Preprint
Article

This version is not peer-reviewed.

Parental Low Level of Education and Single-Parent Families as Predictors of Poor Control of Type 1 Diabetes in Children Followed in French Guiana

A peer-reviewed version of this preprint was published in:
International Journal of Environmental Research and Public Health 2025, 22(7), 1051. https://doi.org/10.3390/ijerph22071051

Submitted:

29 January 2025

Posted:

30 January 2025

You are already at the latest version

Abstract

This study aimed to determine the incidence of type 1 diabetes in French Guiana and describe the social profiles of the patients. We conducted a multicenter cross-sectional study of children under 18 years who were diagnosed with type 1 diabetes and followed up from 2002 to 2021. Over a 20-year period, 48 children under 18 years with type 1 diabetes living in French Guiana were included in the study, out of a total of 59 cases. The study included 26 girls and 22 boys. The incidence rate was 5.9 per 100,000 people in 2018. The mean age at diagnosis was 8.52 years. The age group 5-9 years was the most affected (43.7%). Of these children, 56.2% lived in single-parent households. 35% of the parents had primary education. Of the children, 29.1% were from families with no resources. Diabetes was diagnosed by ketoacidosis in 56.2% of the patients, which was more common than polydipsia in 25% of the patients. Forty% of the patients had an HbA1c >9%. The imbalance (HbA1c>9%) was greater in children whose parents had a low level of education (18.7%) compared with 6% of children whose parents had a university degree and in children from single-parent families (22.9%) compared with children whose parents lived in couples (8%). The 10-14 age group (18.7%) had the highest imbalance. 92% of the patients were treated with a multi-injection insulin regimen, compared to 8% who used an insulin pump. The only chronic complications were retinopathy and diabetic nephropathy.

Keywords: 
;  ;  ;  ;  ;  

Introduction

In its classic form, type 1 diabetes mellitus (T1DM) is characterized by absolute insulin deficiency due to the specific destruction of insulin-secreting beta cells of the pancreas without affecting the other endocrine cells of the pancreas, particularly glucagon-secreting alpha cells. The most plausible mechanism for this destruction is an autoimmune response [1].
Clinically, type 1 diabetes is characterized by cardinal syndrome, which combines polyuria, polyphagia, polydipsia, and weight loss. There was also a break in the weight curve, secondary enuresis, and ketoacidosis in 48% of cases. It is characterized by chronic hyperglycemia with fasting blood glucose >126 mg/dl, blood glucose at any time >200 mg/dl, and the presence of autoantibodies (anti-Langerhans islets, anti-GAD, anti-IA2, anti-insulin, anti-ZnT8) [2].
Type 1 diabetes is the most common chronic disease in children. Worldwide, it accounts for 5-10% of all diabetes cases and 90% of diabetes cases in children. In France, the prevalence is estimated at 19.1/100,000 people [3]. There were 2,500 cases of type 1 diabetes in children aged between 6 months and 14 years. In French Guiana, the prevalence was 3.6/100,000 inhabitants between 2013 and 2015 [4].
This study aimed to determine the incidence of type 1 diabetes in French Guiana and describe the social profile of patients.

Methods

Scope of the Study

French Guiana is a French territory located in South America between Suriname to the west and Brazil to the east. Its population is ethnically diverse and includes Amerindians, blacks, whites, Hispanics, Asians, and mestizos. Approximately 32.6% of the population are aged between 0 and 14 years. There is a high level of vulnerability; the poverty rate is–34-74%. The unemployment rate was 32% (for the 15-64 age group). Only 32.8% of the population over the age of 18 years attended school. Of the working population, 47.4% had no qualifications and 13.2% had a General Certificate of Secondary Education. 44% of families were single-parent families (38% of women lived alone with their children). There is massive immigration from neighboring countries.

Study Design

This is a cross-sectional study. The study population consisted of children aged < 18 years who were diagnosed and followed up in French Guiana. Eleven patients were excluded due (relocation of holidaymakers). The study period spanned from 2002 to 2021 (20 years). This was a multicenter study (Cayenne Hospital and West French Guiana Hospital at Saint-Laurent-du-Maroni).

Data Collected

The data collected were:
Clinical data: age, sex, age at diagnosis, treatment regimen, follow-up, HbA1c, search for complications (retinopathy, nephropathy), other autoimmune diseases, and so on.
-A questionnaire (see supplementary data) was used to collect certain sociodemographic data: employment, parents' level of education, family situation, and social security coverage.
Regular follow-up was defined as visits to a specialist every 3 months.

Data Analysis

Data were entered into an Excel 2016 database and then anonymized. STATA 16.0 software (Stata Corp LP, College Station, TX, USA) was used for all descriptive analyses. The first and third quartiles and the median were used to classify quantitative variables according to statistical criteria. Student's t-test was used for quantitative variables and CHI2 test or Fisher's exact test for qualitative variables. Logistic regression was performed to examine covariates and their associations with outcomes, based on the crude Odds ratio and its confidence interval. If the p-value was less than 0.05, the result was considered to be significant.

Ethics and Consent

This study was based on existing healthcare data. These data were extracted from the hospital databases. It was approved by the ethics committee of the Centre Hospitalier de Cayenne under the number 0013/2022. However, parents and patients were informed of the use of their data by an information poster in pediatric units. All parents and patients were personally informed and asked to provide consent to participate in the study. All data were collected after certification of the patients’ written non-opposition. All participants who were minors provided written informed consent from their parents or legal guardians. We also obtained parents' consent to publish their children's clinical data. Data were anonymized according to the French legislation (Loi no. 78-17 du 6 janvier 1978 relative à l’informatique, aux fichiers et aux libertés modifiée). The study was registered with the hospital's Data Protection Office (DPO) and published on the HDH summary FDATAHUB site. According to the European regulation, French observational studies from data obtained routinely, from patient health-care records, do not need the approval of an ethics committee [5,6].

Results

Over a period of 20 years, we recorded 59 children under the age of 20 years with type 1 diabetes in French Guiana. Eleven patients were excluded because their main residence was not in French Guiana. Data from 48 patients living in French Guiana were included in the study. The study included 26 girls and 22 boys.

Epidemiological Data

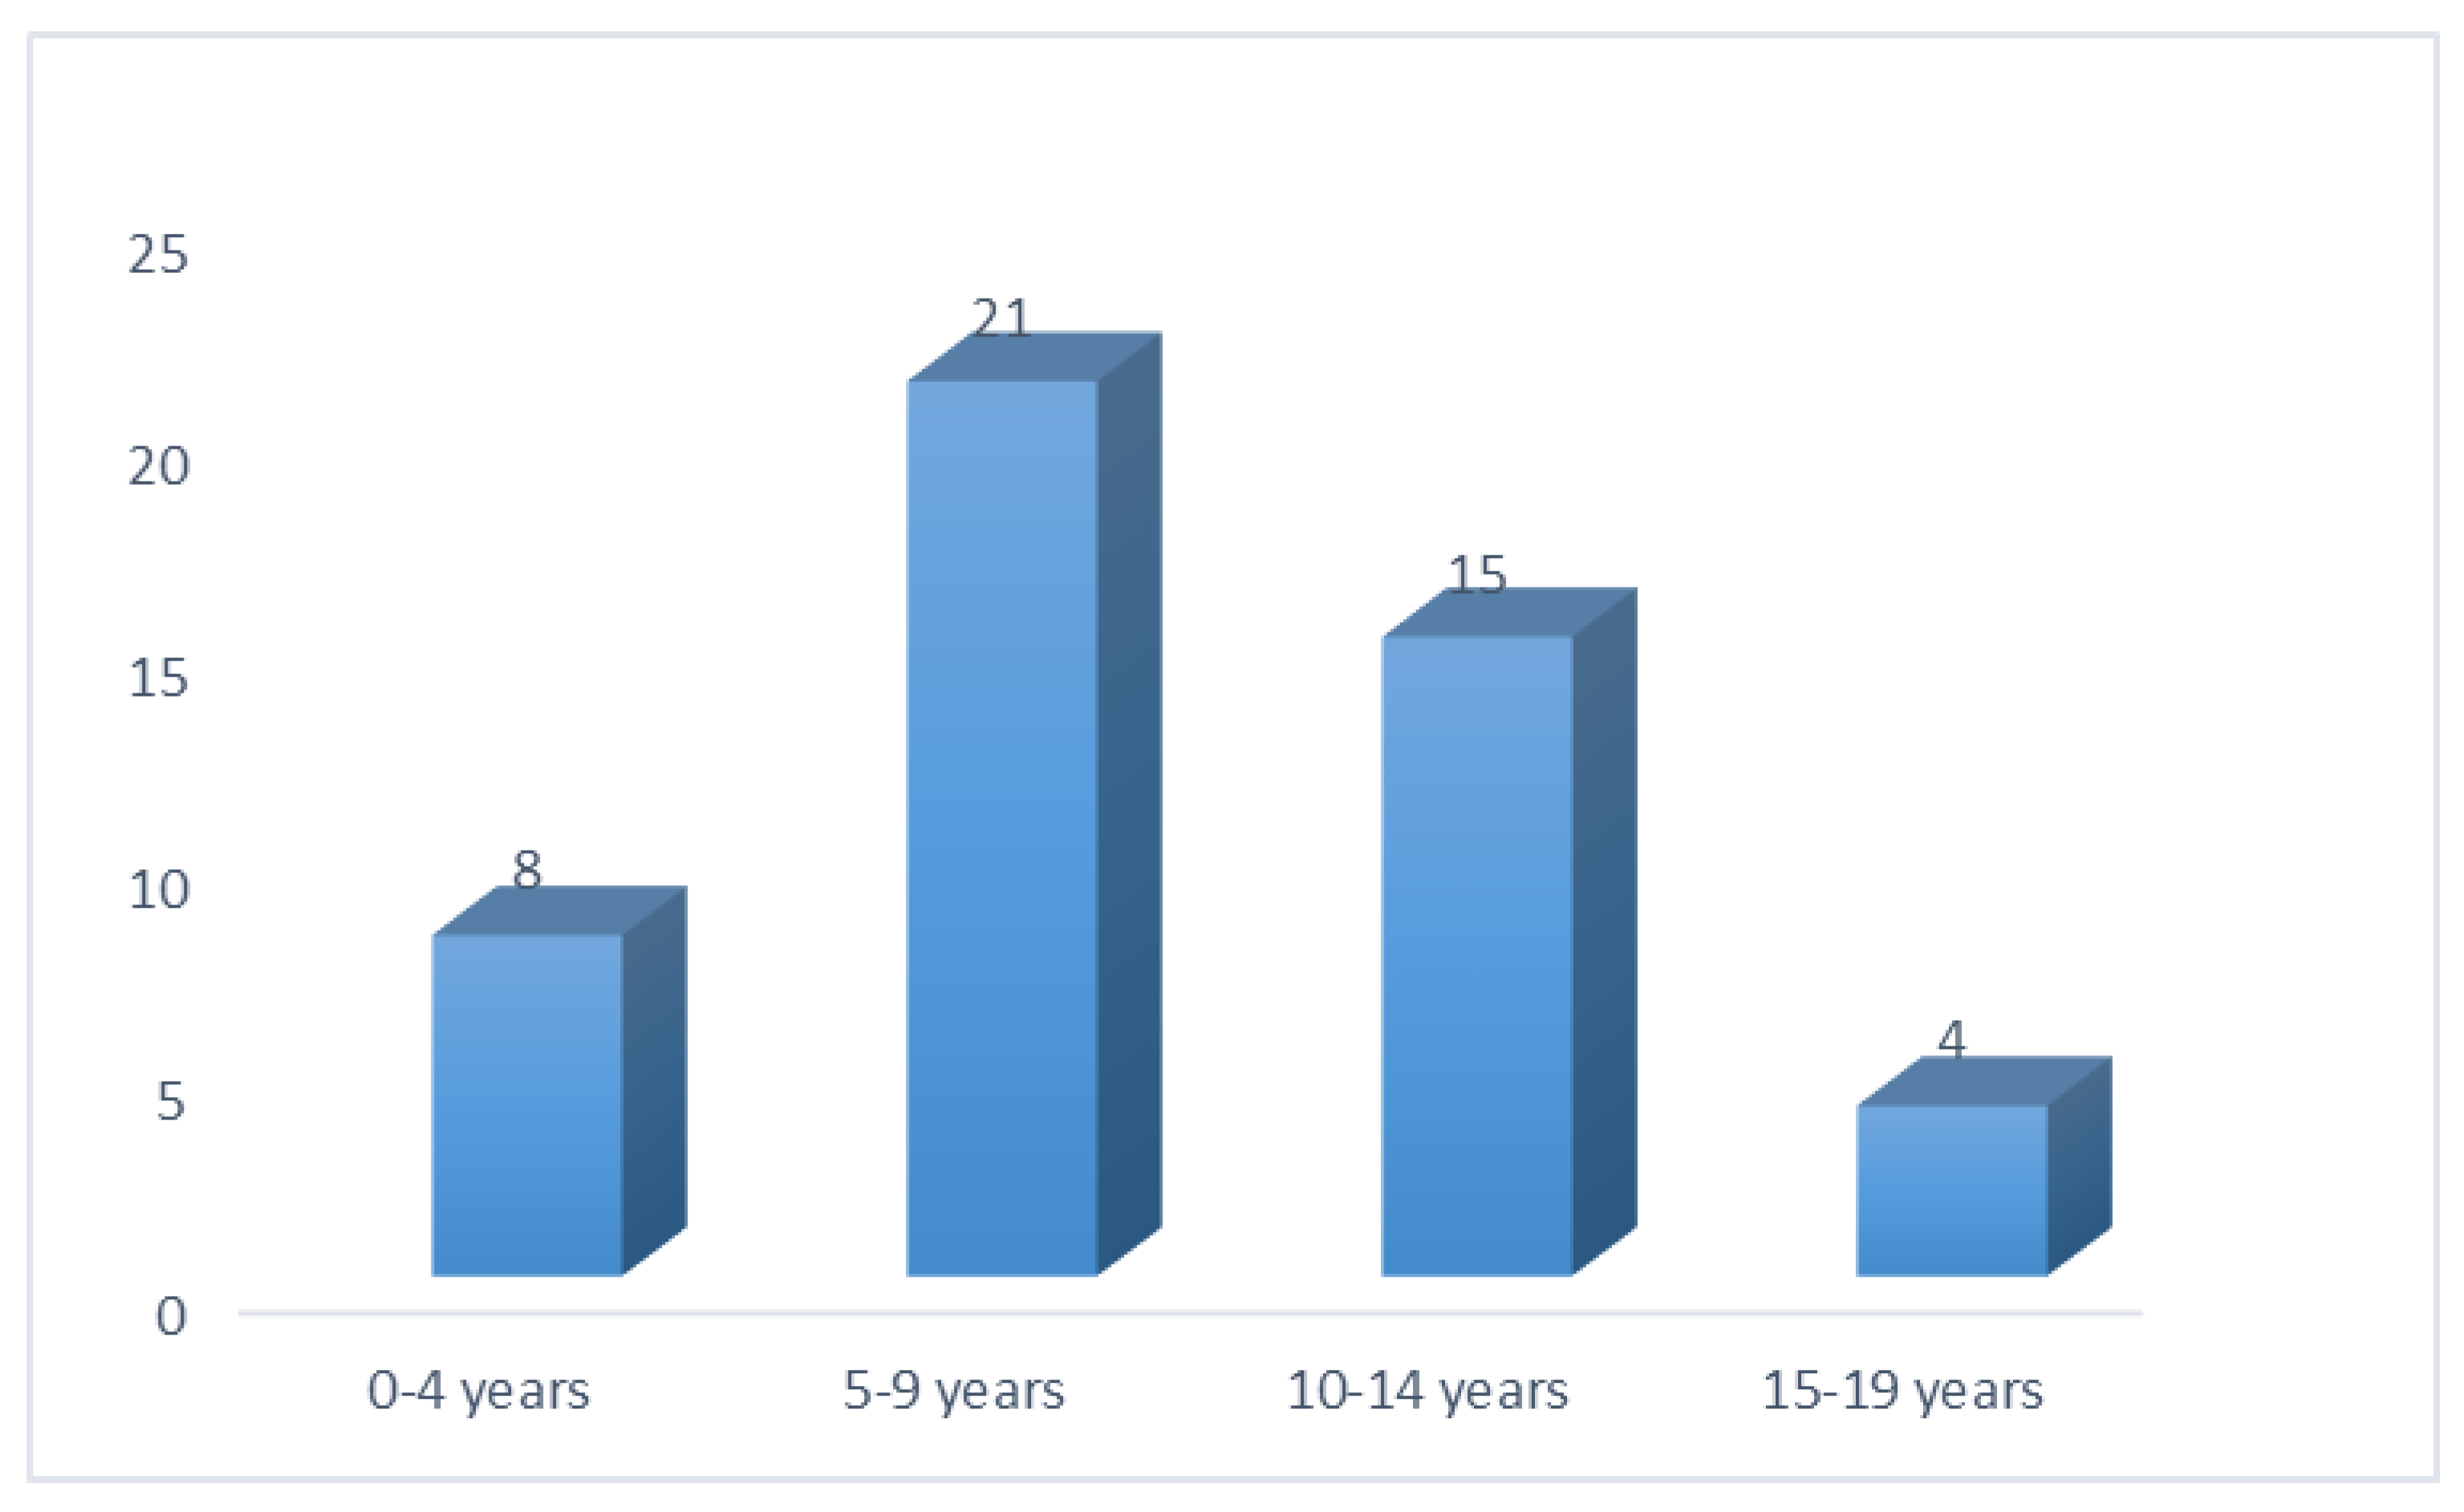
Based on all the data, the incidence was 5.9 per 100,000 population in 2018. The annual incidence varies from one case per year in 2002 to 10 cases per year in 2021. Therefore, it has increased significantly over the years (Figure 1). The mean age at diagnosis was 8.52 years. The 5-9-year age group was the most affected (43.7%) (Figure 2).

Social Data

In French Guiana, 56.2% of the children with diabetes lived in single-parent families. The imbalance was greater in single-parent families (36.6%) than in children whose parents lived with a couple (13.3%). 35% of parents of children with type 1 diabetes have primary education. Of the children, 29.1% came from families with no resources or living with assistance (relatives or associations). Of the children, 20.8% had no social security coverage at the time of diagnosis. Of our patients, 66.6% had regular follow-up compared to 29.6% who had irregular follow-up. The follow-up was more irregular if the parents had a low level of education. However, having a job did not influence the quality of follow-up.

Clinical Data

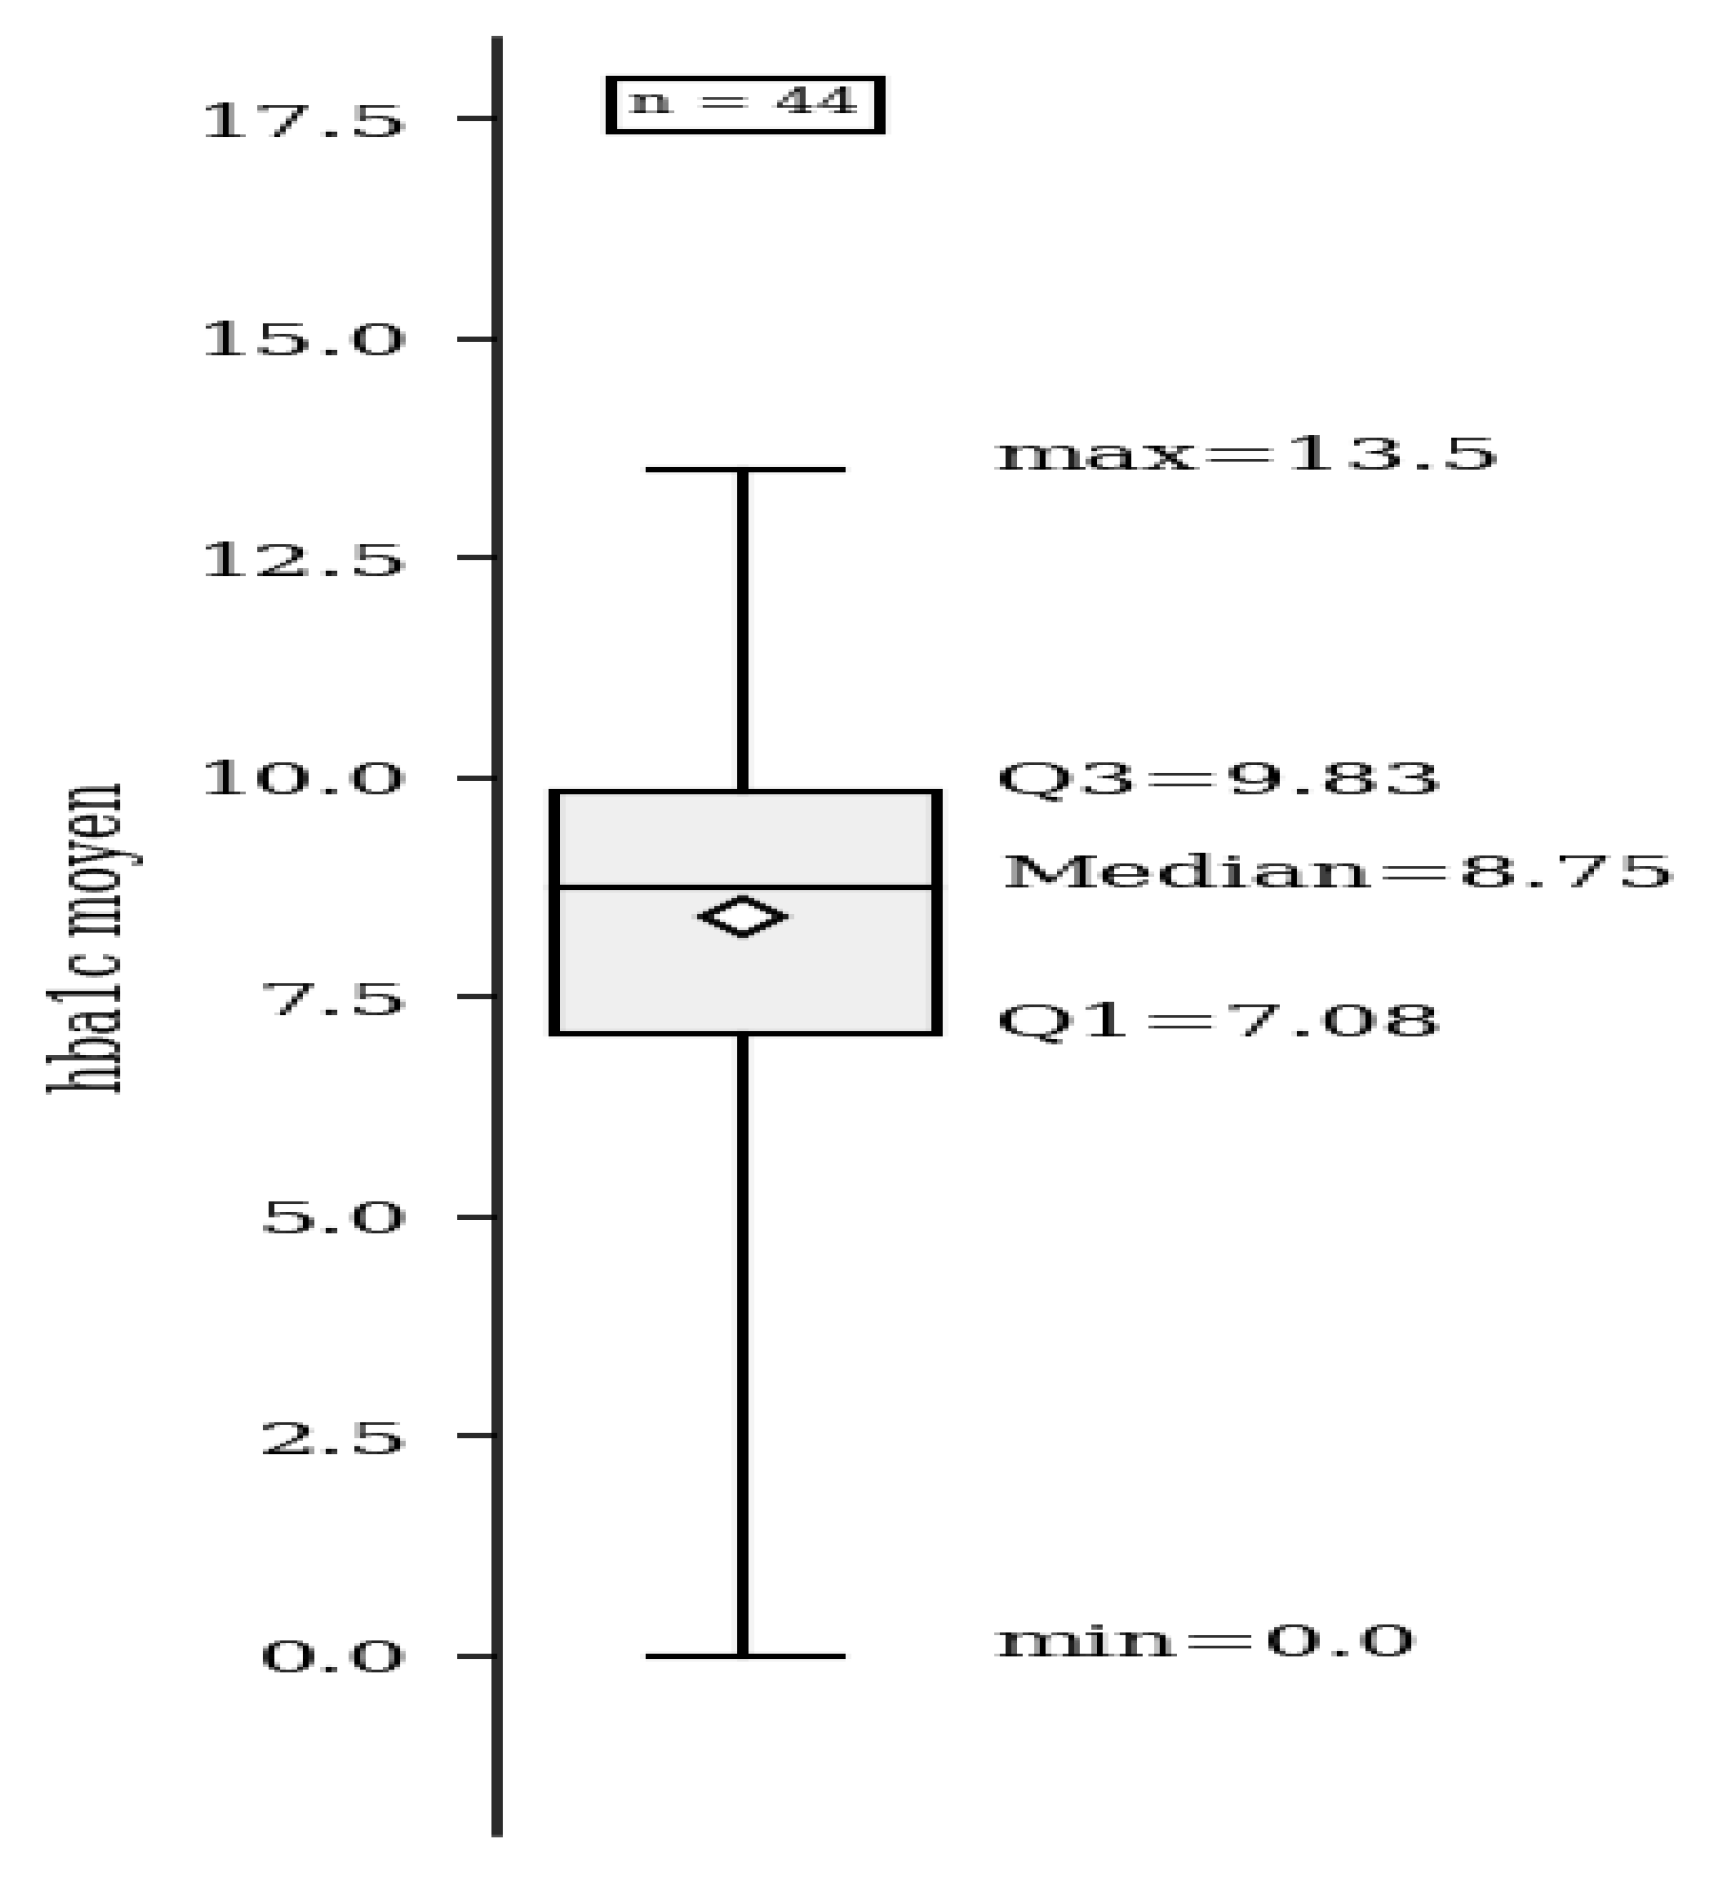
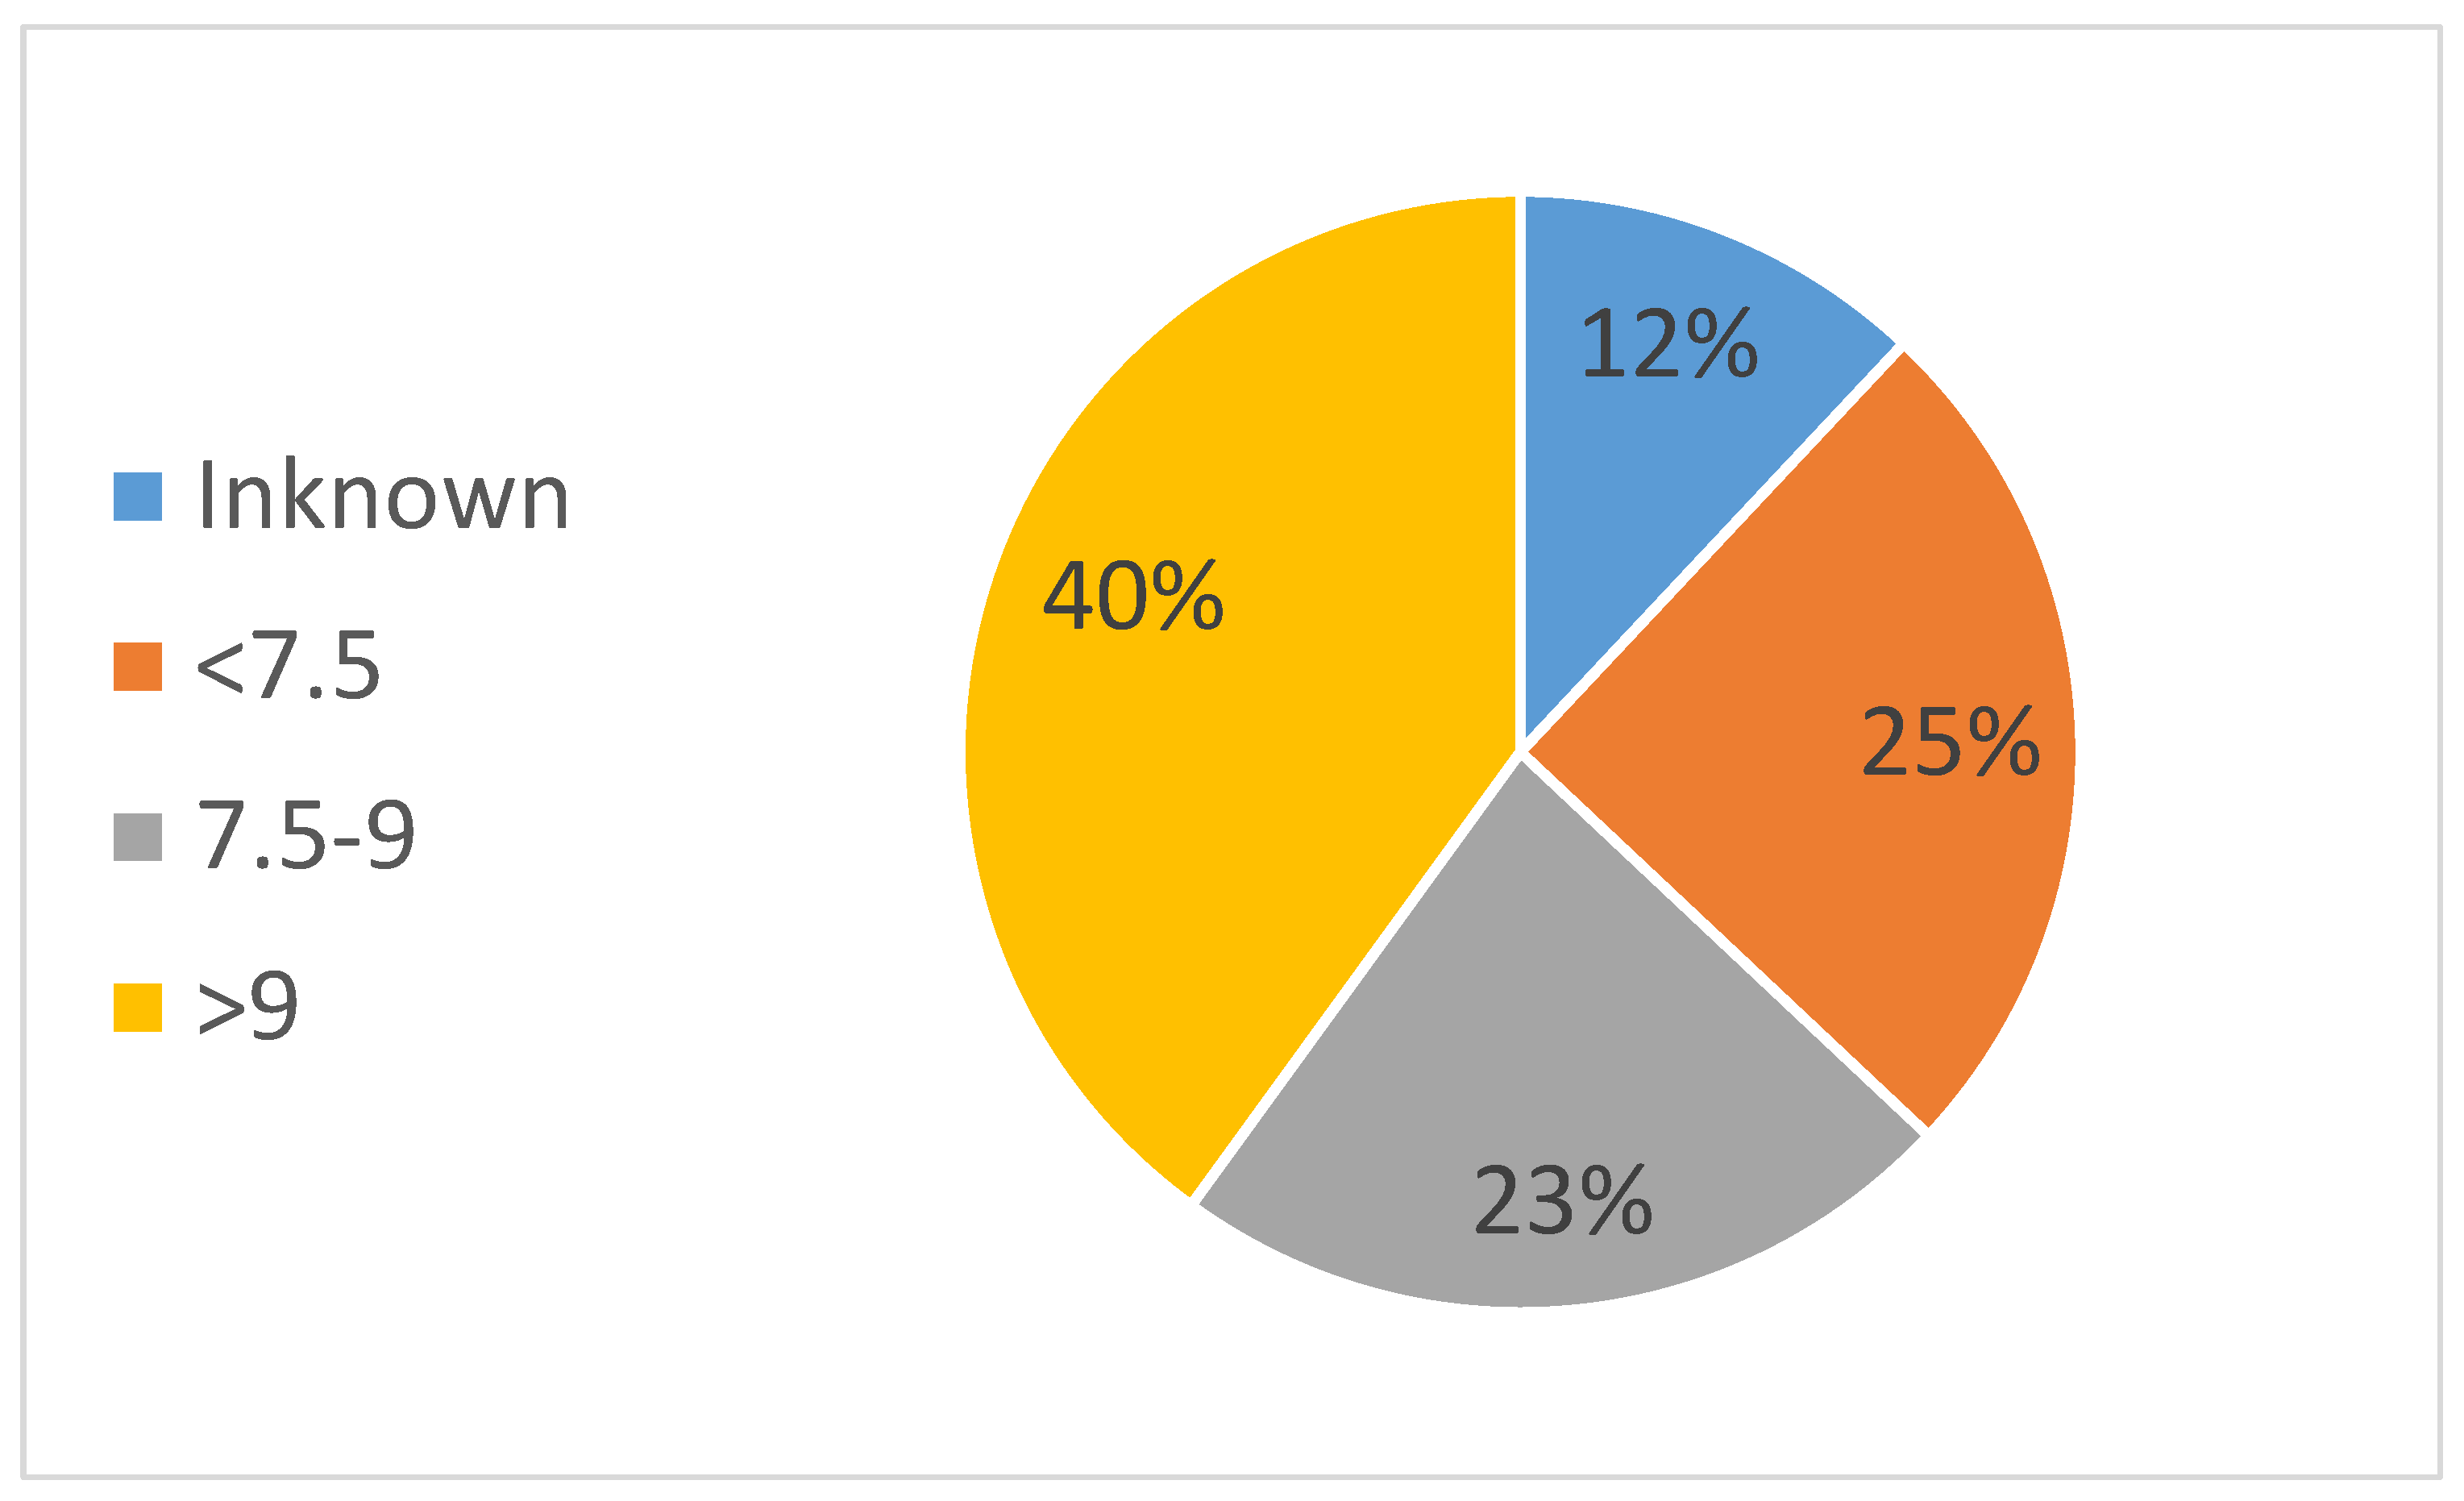
Diabetes was detected as ketoacidosis in 56.2% of patients, which was more common than polydipsia in 25% of patients. The HbA1c level was within the target range of <7.5%. Glycemic control in our cohort was unsatisfactory, with a median glycemic hemoglobin level of 8.7% (Figure 3). Only 25% of the patients had HbA1c levels within the target range. 63% of our patients had HbA1c levels outside the target range. Forty% of the patients had an HbA1c >9%. (Figure 4).
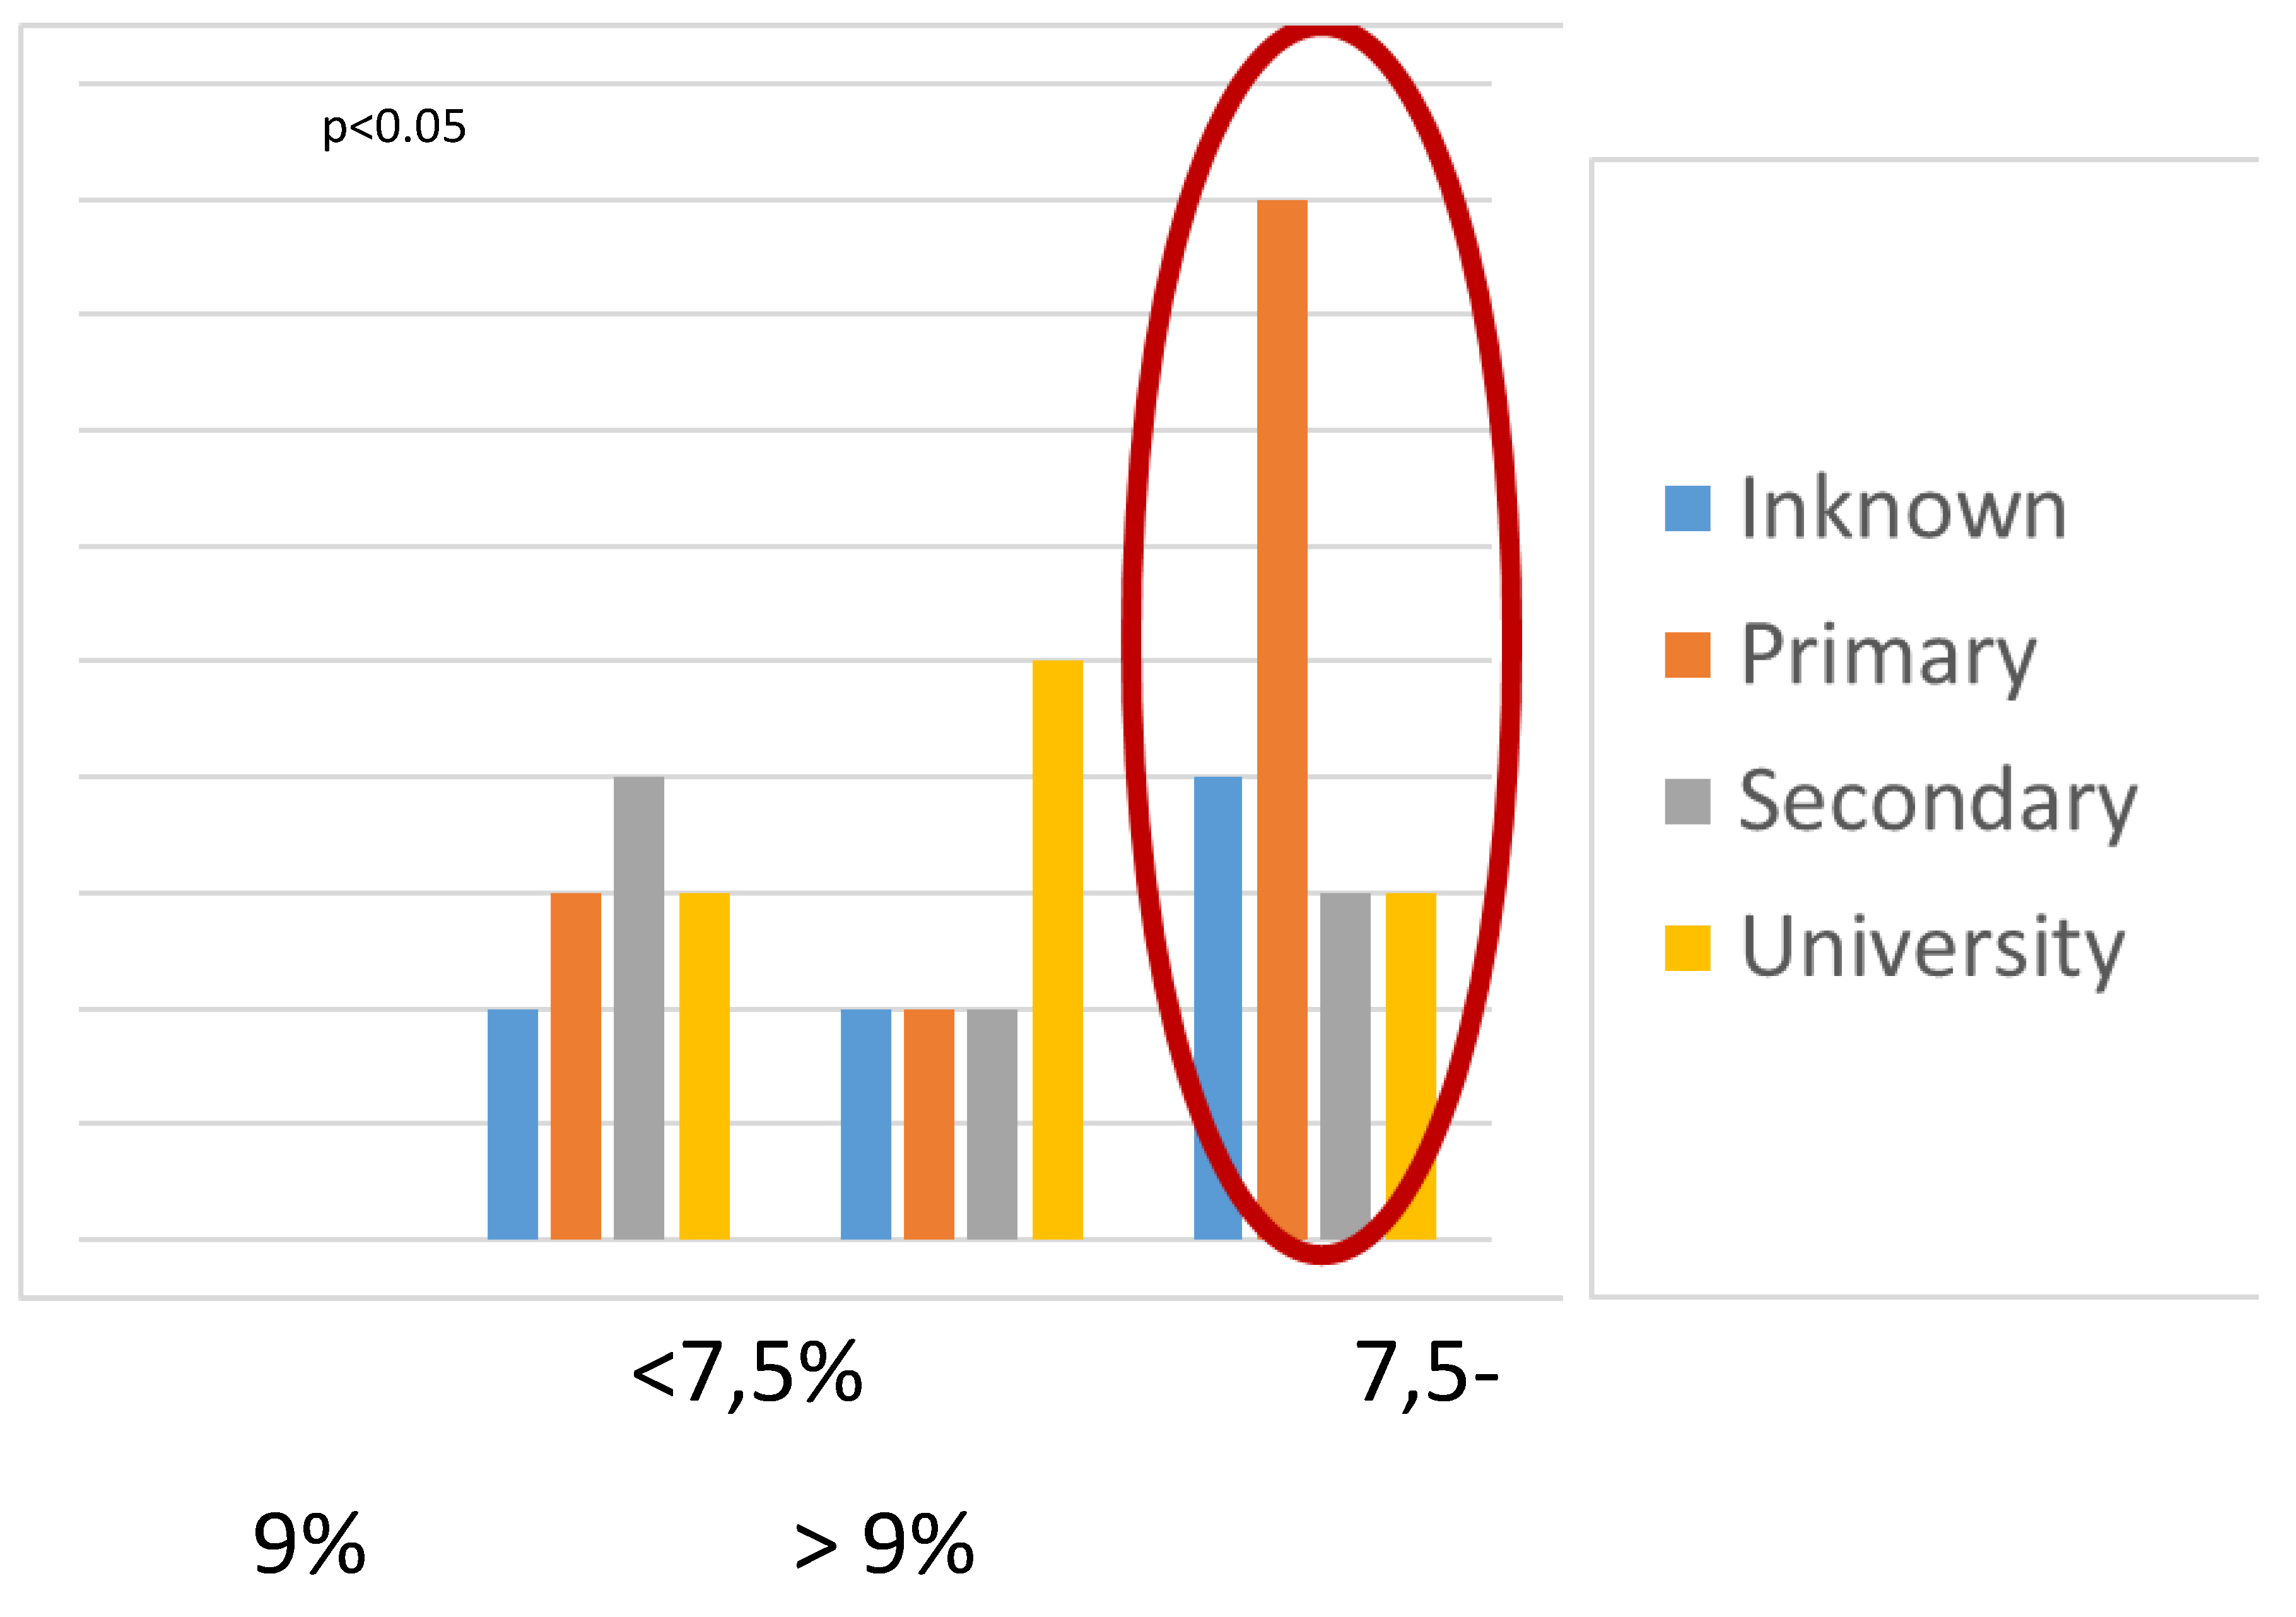
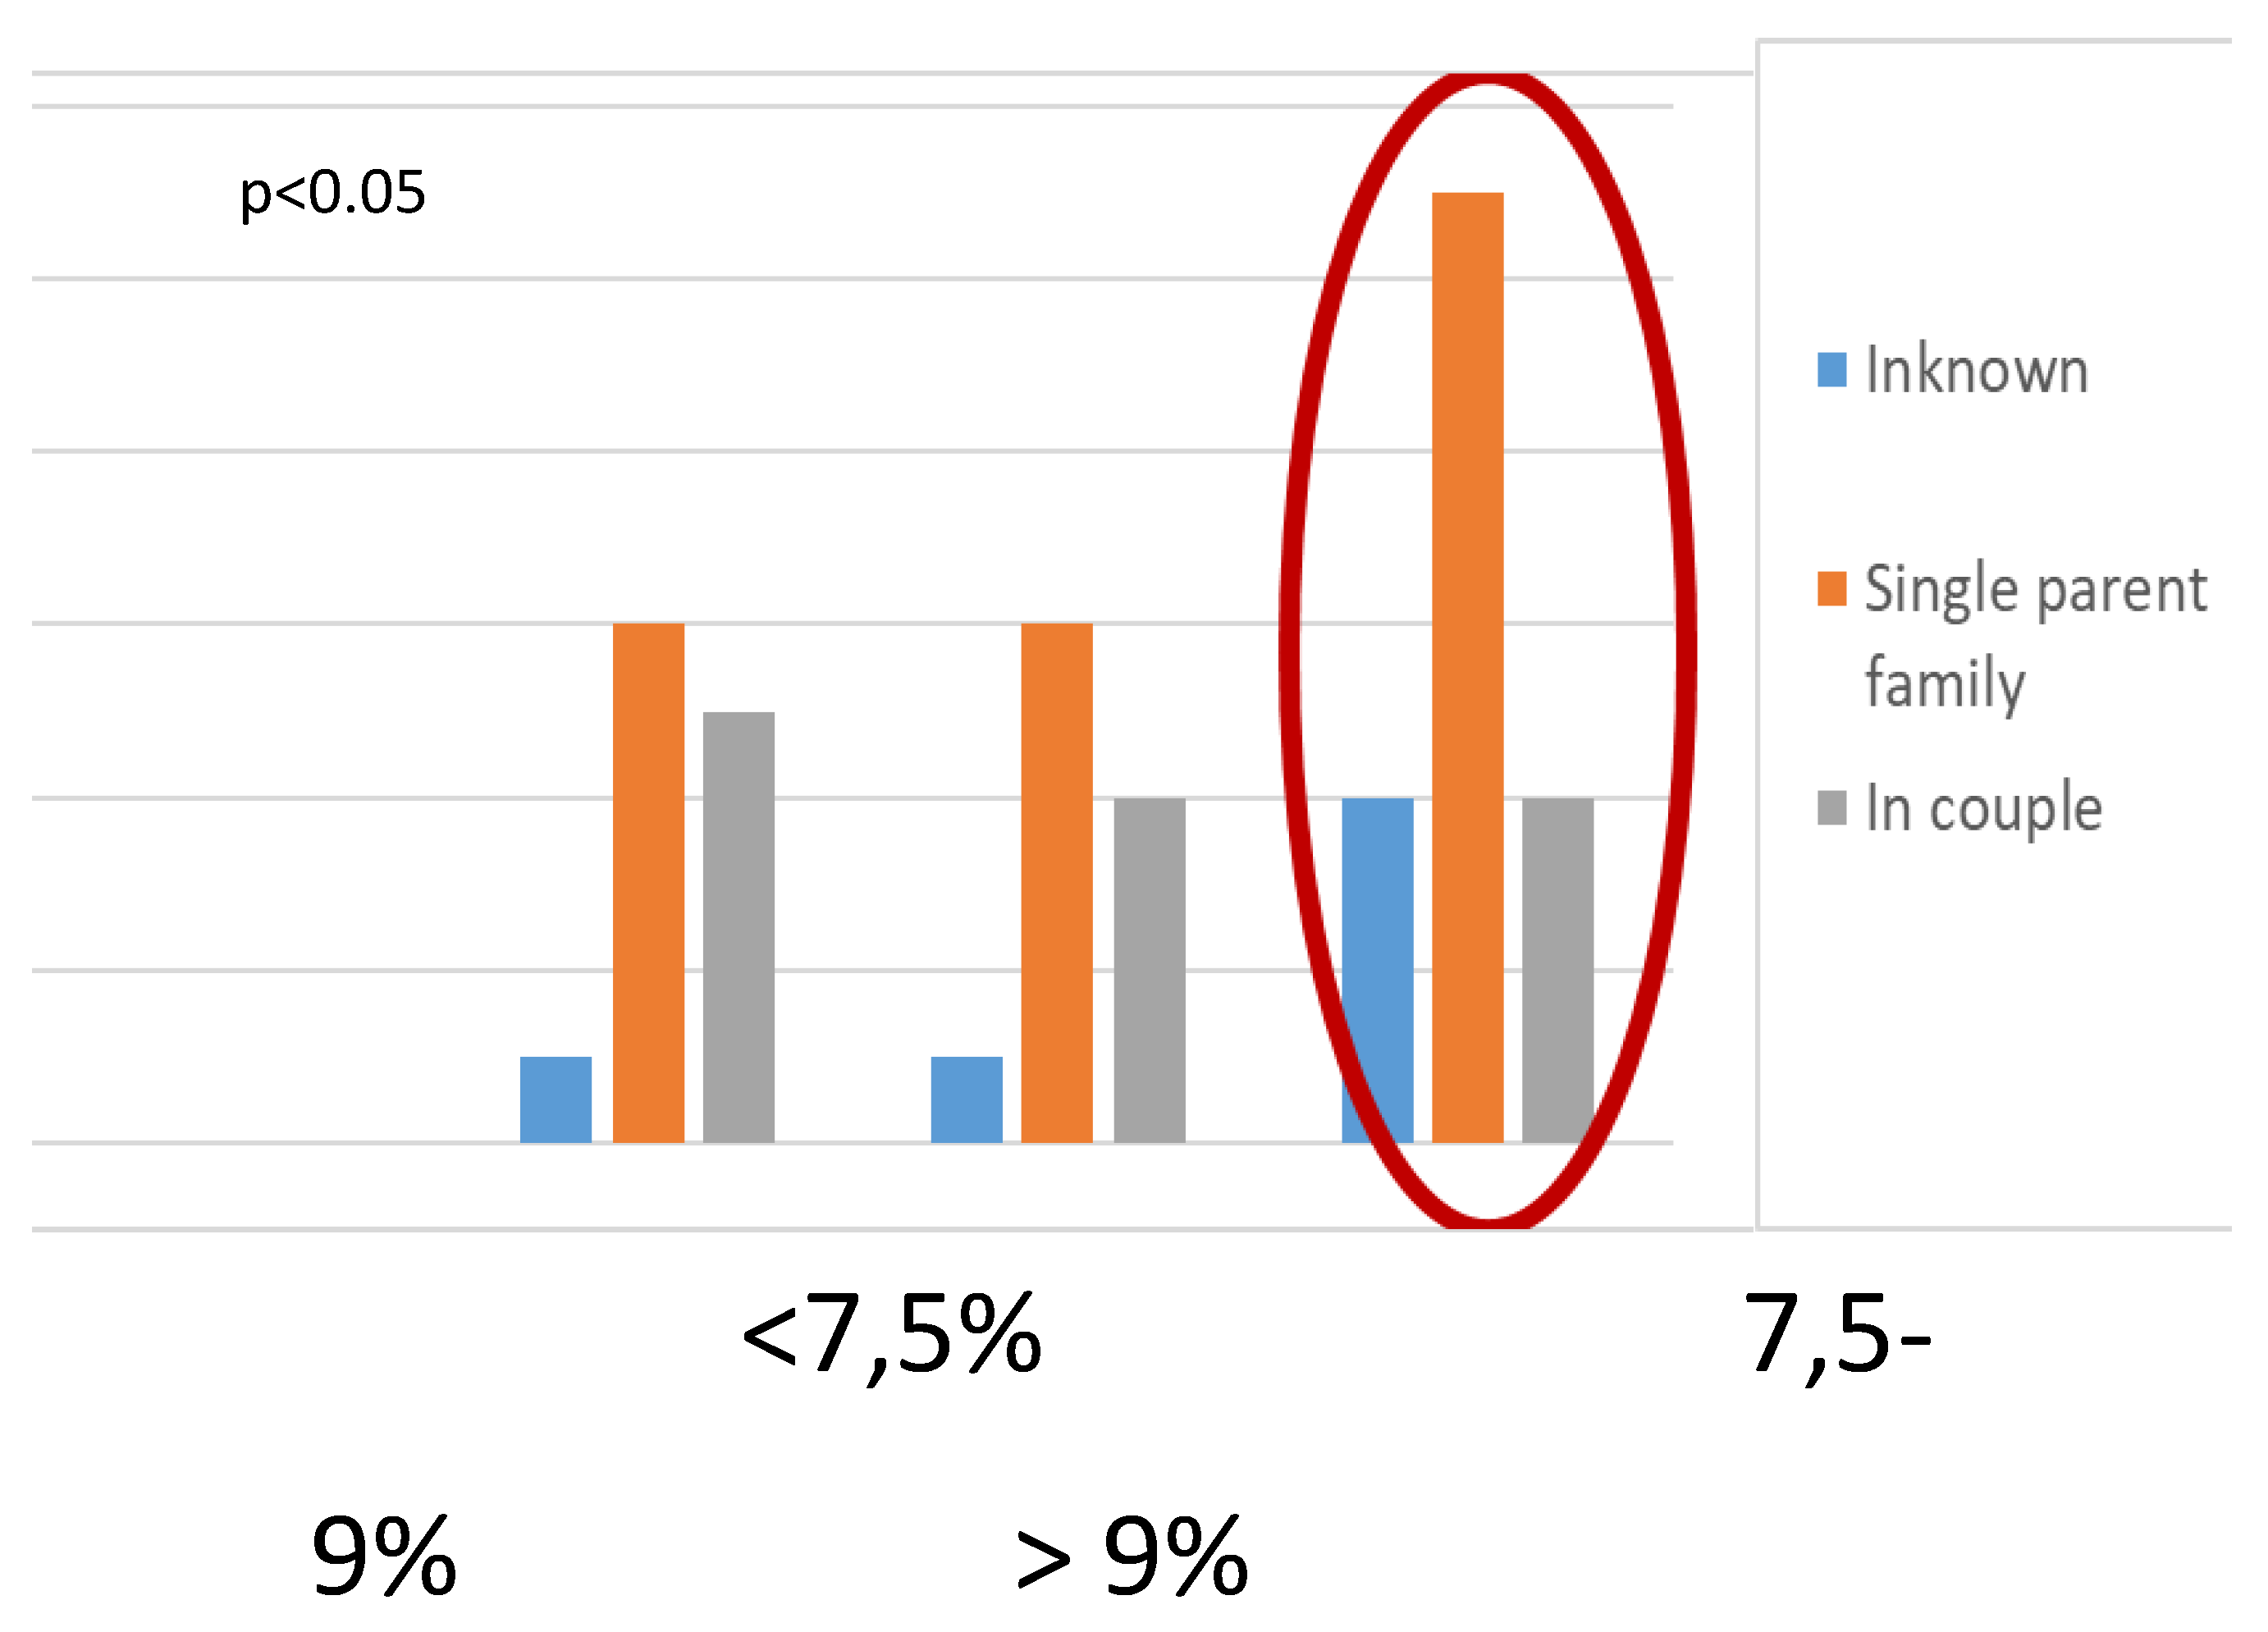
The imbalance was greater (HbA1c>9%) when the parents had a low level of education (18.7%) compared with 6% of children whose parents had a university degree (Figure 5) and in children from single-parent families (22.9%) compared with children whose parents lived in a couple (8%) (Figure 6). The 10-14 age group (18.7%) had the highest imbalance. 92% of our patients were treated with a multiinjection basal-bolus insulin regimen, compared with 8% using an insulin pump.
Of the patients, 45.8% were home nurses. This was because it was difficult for the family to check the blood glucose levels and administer treatment. No other autoimmune diseases were found in any of the patients at the time of diagnosis. The only chronic complications examined were retinopathy and diabetic nephropathy. Among our patients, 4.1% had diabetes for at least 10 years. No complications were observed in any of these patients.

Discussion

The incidence of T1DM in our study population was 5.9 cases/100,000 inhabitants by 2021. Between 2013 and 2015, a French study tasked with determining the incidence in the regions of France estimated the incidence in French Guiana at 3.6 cases per 100,000 [3]. This study had limitations, as the data were not collected in the field, but from the national health data system database. This rate was lower than that in other regions of metropolitan France (12.6 in Pyrénées Orientales, 15.8 in Pays de la Loire, 17.9 in Ile de France and 21.7 in Corsica) [4,7,8]. It was also the lowest rate in the French overseas departments: 12.2 in Guadeloupe, 11.35 in Martinique and 14.2 in Réunion between 2013-2015[3,4,9]. This result corroborates the fact that the incidence rate of T1DM in French Guiana was the lowest in France.
In the South American region, however, the rate is higher than that in Colombia (3.8% in the under-14s [10] or Venezuela 0.1 per 100,000 [11]. This was much lower than Brazil's rate of 10-20 per 100,000 people [9]. Children with type 1 diabetes in this region represent only 0.2% of the total population with diabetes [12].
Despite these low rates, its incidence has been increasing over the years. These results are in line with the fact that type 1 diabetes is increasing worldwide [9,11,12] and French Guiana is no exception. The DIAMOND study showed an overall upward trend of 2.8% per year [8,13]. The increase in the incidence rate in French Guiana could be attributed to the emigration of healthy people and the immigration of vulnerable people from neighboring countries in search of a better socio-economic or health situation, respectively.
Women predominated in our study, and this result is not consistent with that of previously published studies.
The mean age at diagnosis was 8 years; a similar figure was found in the PEDIA-LR register (5). This is slightly lower than the 9.9 years found in 2007 in the United States of America (USA) [13].
Over 20 years, the most affected age group was 5-9 years. Several studies have found a higher rate in the under-4 years and in–10-14 age group [14,15].
As in the SEARCH study, we did not observe a decrease in age at diagnosis over the years [9], unlike the results of a study in Guadeloupe, which found a higher incidence in the 0-4 age group (30%) than in the 5-9 age group (6.7%) and the 10-15 age group (1.6%) [9]. Diabetic ketoacidosis was observed in 56% of cases. PEDIA-LR showed a significant increase in the incidence of ketoacidosis in children under 5 [7]. This is a significant finding. A French cohort study carried out by « Aide aux jeunes diabétiques » (AJD) in 2009, as part of a campaign to prevent ketoacidosis, found that 44% of subjects disclosed their disease through this complication. This clinical condition is still the most common cause of type 1 diabetes [7,8,14]. This shows that more needs to be done to identify other warning signs at an early stage so that the alarm can be sounded as soon as the cardinal syndrome appears. Blanc et al. showed that there is a greater risk of ketoacidosis in children from households with a low monthly income [14].
In our study, the mean HbA1c level was 8.7%, reflecting poor glycemic control. A similar rate was found by the AJD in 2011 [15]. In our study, the independent predictive factors of high HbA1c were low parental level of education and single-parent families. The literature has identified several factors associated with high HbA1c levels, including adolescence, low socioeconomic status, low parental education, single-parent family structure, diabetes-related family conflict, lower parental involvement in diabetes care, and lack of a regular diabetes care provider [16,17,18,19]. Most of our children (56.2%) lived in single-parent families. This reflects Guianese society, where 44% of families are single-parent families [20]. The lower the socioeconomic level or level of education, the higher is the HbA1c level. A total of 18.7% of our patients, whose parents had a low level of education, had an HbA1c level >9%. The SEARCH study reported a rate of 17% in children with Hba1c>9.5%.
Twenty-three percent (n=11) of our patients had no regular follow-up, including (n=7) whose parents had a low level of education. Similar trends have been reported in the literature. A low level of education is a risk factor for poor follow-up and glycemic control [17,19]. On the other hand, whether the parents were employed did not affect follow-up. This finding is similar to that of the Gomes study in Brazil. The number of visits to specialists, irrespective of economic status (3.8 ± 1.3 vs. 4.1 ± 1.5 vs. 4.2 ± 1.5 vs. 4.3 ± 1.7 for high, medium, low and very low). Similarly, the absence of social security coverage at diagnosis did not affect the quality of follow-up. Unfortunately, the notion of diabetes-related family conflict was not investigated in our study.
The dominant insulin therapy regimen in our study was a multiinjection system. This differs from the insulin pump, which is currently the most widely used model in other regions (49.9% in Aquitaine) [21]. Data in the literature show that the insulin pump has several advantages [22,23]:i) reduced number of complications, ii) best method of mimicking physiological insulin secretion, iii) method of choice for children under the age of 6, iii) improved quality of life by reducing the number of injections and severe hypoglycemia, and iiiii/ improved night-time control (blood glucose levels at bedtime, in the middle of the night, and on rising) compared with a regimen involving multiple injections of insulin. This highly specialized technique requires rigorous education and numerous precautions. Several factors may explain why the pump is virtually not used in French Guiana: the low level of education of parents, lack of trained staff, and reluctance of families. However, we believe that a feasibility study should be conducted to determine the reasons for this finding. Nevertheless, the insulin pump cannot be offered to everyone, and therefore, its use must refer to official recommendations. The presence of complications is associated with the duration of diabetes has been present. Complications are more frequent when diabetes has been present for at least 10 years [22]. The risk also increases in patients with poor glycemic control [25]. However, its incidence varies. In the case of diabetic retinopathy, a French study reported a prevalence of 4.6% [26]. This may be due to both hormonal changes and poorer glycemic control after puberty [14,25,26,27,28,29]. Only 2 children had diabetes for 10 years. We did not record any case of diabetic retinopathy. It is difficult to draw conclusions from this small number of children.

Limitations of Our Study

However, we recognize certain limitations of our study. Although the entire pediatric population with type 1 diabetes was included, our sample size was quite small. Another limitation was the retrospective nature of this study. Some patients diagnosed in French Guiana and followed up for a few months were lost to follow-up (relocation), which did not allow us to collect all their social data. The social factors studied were not exhaustive and details of the resources available to them were not provided.

Conclusion

In conclusion, the incidence of type 1 diabetes in children is steadily increasing in French Guiana, similar to that in other regions of France. More than half of our patients had unbalanced diabetes. In French Guiana, a region where the educational level of the population is below the national average, a major effort is needed to detect this condition at an early stage and provide treatment and therapeutic education to families. Addressing the social correlates of poor glycemic control is essential for improving the care of children with type 1 diabetes. We need to promote access to new diabetes management technologies.

Author Contributions

CBSF : Conceptualization, data curation, methodology, resource, formal analysis, writing—original draft preparation, FN : resource, software, data curation, validation, supervision, review and editing, NA : resource, software, data curation, validation, review and editing NE : project administration, investigation, visualization, formal analysis, supervision, review and editing All authors have read and agreed to the published version of the manuscript.

Funding

This research received no specific grants from any funding agency in the public, commercial, or not-for-profit sector.

Data availability

The data that support the findings of this study are available in raisonable request.

Conflicts of interest

The authors declare that this research was conducted in the absence of any commercial or financial relationships that could be construed as potential conflict of interest.

Abbreviations

T1DM
Type 1 diabetes mellitus
DPO
Data Protection Office
USA
United States of America
AJD
Aide aux jeunes diabétiques

References

  1. Desai S, Deshmukh A. Mapping of Type 1 Diabetes Mellitus. Curr Diabetes Rev. 2020;16(5):438-441. [CrossRef]
  2. Mayer-Davis EJ, Kahkoska AR, Jefferies C, Dabelea D, Balde N, Gong CX, Aschner P, Craig ME. ISPAD Clinical Practice Consensus Guidelines 2018: Definition, epidemiology, and classification of diabetes in children and adolescents. Pediatr Diabetes. 2018;19 Suppl 27(Suppl 27):7-19. [CrossRef]
  3. Piffaretti C, Mandereau-Bruno L, Guilmin-Crepon S, Choleau C, Coutant R, Fosse-Edorh S. Trends in childhood type 1 diabetes incidence in France, 2010-2015. Diabetes Res Clin Pract. 2019;149:200-207. [CrossRef]
  4. Charkaluk ML, Czernichow P, Lévy-Marchal C. Incidence data of childhood-onset type I diabetes in France during 1988-1997: the case for a shift toward younger age at onset. Pediatr Res. 2002;52(6):859-62. [CrossRef]
  5. Directive 2001/20/EC of the European Parliament and of the Council of 4 April 2001 on the approximation of the laws, regulations and administrative provisions of the Member States relating to the implementation of good clinical practice in the conduct of clinical trials on medicinal products for human use.https://ec.europa.eu/health/sites/...2001_20/dir_2001_20_en.pdf. Accessed 2001.
  6. Toulouse E, Masseguin C, Lafont B, McGurk G, Harbonn A, A Roberts J, Granier S, Dupeyron A, Bazin JE. French legal approach to clinical research. Anaesth Crit Care Pain Med. 2018 ;37(6):607-614.
  7. Epidemiology of diabetes in children in Languedoc-Roussillon (France). Arch Pediatr. 2015 ;22(3):241-6.
  8. Sophie Guilmin-Crépon, Rachel Reynaud. Type 1 diabetes in pediatrics: Public health and epidemiologic point of view. Médecine des Maladies Métaboliques 2020 ; 14(5) : 383-390.
  9. Audrey Montout. Incidence of diabetes mellitus in children aged less than 15 years 3 months in Guadeloupe, from 2000 to 2014: retrospective observational study. Medical thesis from the faculty of Guadeloupe. Paediatrics 2016. ⟨dumas-01317766⟩.
  10. Vargas-Uricoechea H, Casas-Figueroa LÁ. An Epidemiologic Analysis of Diabetes in Colombia. Ann Glob Health. 2015;81(6):742-53.
  11. DIAMOND Project Group. Incidence and trends of childhood Type 1 diabetes worldwide 1990-1999. Diabet Med. 2006;23(8):857-66.
  12. Aschner P, Aguilar-Salinas C, Aguirre L, Franco L, Gagliardino JJ, de Lapertosa SG, Seclen S, Vinocour M; IDF Diabetes Atlas. Diabetes in South and Central America: an update. Diabetes Res Clin Pract. 2014 Feb;103(2):238-43.
  13. Lawrence JM, Imperatore G, Dabelea D, et al. Trends in incidence of type 1 diabetes among non Hispanic white youth in the United States, 2002–2009. Diabetes 2014; 63(11):3938–45.
  14. Sehgal M, Batra M, Jha P, Sanchez O. Risk Factors and Laboratory Findings Associated With Diabetic Ketoacidosis in Hospitalized Pediatric Patients. Cureus. 2022 May 27;14(5):e25410. [CrossRef]
  15. Choleau C, Maitre J, Filipovic Pierucci A, Elie C, Barat P, Bertrand AM, de Kerdanet M, Letallec C, Levy-Marchal C, Nicolino M, Tubiana-Rufi N, Cahané M, Robert JJ; AJD Study Group. Ketoacidosis at diagnosis of type 1 diabetes in French children and adolescents. Diabetes Metab. 2014;40(2):137-42. [CrossRef]
  16. A. Galler, M Lindau, Andrea Ernert, Ralf Thalemann, et Klemens Raile. Associations Between Media Consumption Habits, Physical Activity, Socioeconomic Status, and Glycemic Control in Children, Adolescents, and Young Adults With Type 1 Diabetes. Diabetes Care 2011; 34: 2356–2359. [CrossRef]
  17. Fantahun B, Leulseged TW. Glycemic control among children with type 1 diabetes mellitus and its determinants in a resource-limited setting. J Pediatr Endocrinol Metab. 2022;35(6):813-817. [CrossRef]
  18. Snyder LL, Stafford JM, Dabelea D, Divers J, Imperatore G, Law J, Lawrence JM, Pihoker C, Mayer-Davis EJ. Socio-economic, demographic, and clinical correlates of poor glycaemic control within insulin regimens among children with Type 1 diabetes: the SEARCH for Diabetes in Youth Study. Diabet Med. 2019 ;36(8):1028-1036. [CrossRef]
  19. Gomes MB, Rodacki M, Pavin EJ, Cobas RA, Felicio JS, Zajdenverg L, Negrato CA. The impact of ethnicity, educational and economic status on the prescription of insulin therapeutic regimens and on glycemic control in patients with type 1 diabetes. A nationwide study in Brazil. Diabetes Res Clin Pract. 2017;134:44-52. [CrossRef]
  20. Full report - Department of French Guiana (973) | Insee https://www.insee.fr/fr/statistiques/2011101?geo=DEP-97.
  21. Campas-Lebecque MN, Pochelu S, Vautier V et coll, Bacheré N, Beau C, Benoit M, Cammas B, Carré M, Chevrel J, Compain F, Fargeot-Espaliat A, Franc M, Galtier A, Gambert C, Lacoste A, Lienhardt A, Martineau L, Oilleau L, Percot-Blondy M, Tamboura A, Valade A, Barat P -Do children and adolescents with type 1 diabetes suffer from a lack of resources in France? Results from a benchmark study in the New Aquitaine region. Arch Pediatr. 2021;28(4):301-306.
  22. Danne T, Phillip M, Buckingham BA, Jarosz-Chobot P, Saboo B, Urakami T, Battelino T, Hanas R, Codner E. ISPAD Clinical Practice Consensus Guidelines 2018: Insulin treatment in children and adolescents with diabetes. Pediatr Diabetes. 2018 ;19 Suppl 27:115-135.
  23. Radermecker RP, Hermans MP, Legrand DA, Scheen AJ. L'insulinothérapie par pompe externe à perfusion continue d'insuline [Continuous subcutaneous insulin infusion with portable pumps]. Rev Med Liege. 2005;60(5-6):329-34.
  24. Tienhaara E, Falck AAK, Pokka TM, Tossavainen PH. The natural history of emerging diabetic retinopathy and microalbuminuria from prepuberty to early adulthood in Type 1 diabetes: A 19-year prospective clinical follow-up study. Diabet Med. 2022 ;39(1):e14732. [CrossRef]
  25. Perais J, Agarwal R, Evans JR, Loveman E, Colquitt JL, Owens D, Hogg RE, Lawrenson JG, Takwoingi Y, Lois N. Prognostic factors for the development and progression of proliferative diabetic retinopathy in people with diabetic retinopathy. Cochrane Database Syst Rev. 2023 ;2(2):CD013775. [CrossRef]
  26. Lassmann-Vague V, Clavel S, Guerci B, Hanaire H, Leroy R, Loeuille GA, Mantovani I, Pinget M, Renard E, Tubiana-Rufi N; Société francophone du diabète (ex ALFEDIAM). When to treat a diabetic patient using an external insulin pump. Expert consensus. Société francophone du diabète (ex ALFEDIAM) 2009. Diabetes Metab. 2010;36(1):79-85. [CrossRef]
  27. Massin P, Erginay A, Mercat-Caudal I, Vol S, Robert N, Reach G, Cahane M, Tichet J. Prevalence of diabetic retinopathy in children and adolescents with type-1 diabetes attending summer camps in France. Diabetes Metab. 2007;33(4):284-9. [CrossRef]
  28. Zabeen B, Khaled MZ, Husain L, Aktar A, Huda K, Kamal YA, Choudhury N, Azad K. Risk factors associated with retinopathy in young people with type 1 diabetes in Bangladesh. Endocrinol Diabetes Metab. 2020 ;4(2):e00197. [CrossRef]
  29. Tommerdahl KL, Shapiro ALB, Nehus EJ, Bjornstad P. Early microvascular complications in type 1 and type 2 diabetes: recent developments and updates. Pediatr Nephrol. 2022;37(1):79-93. [CrossRef]
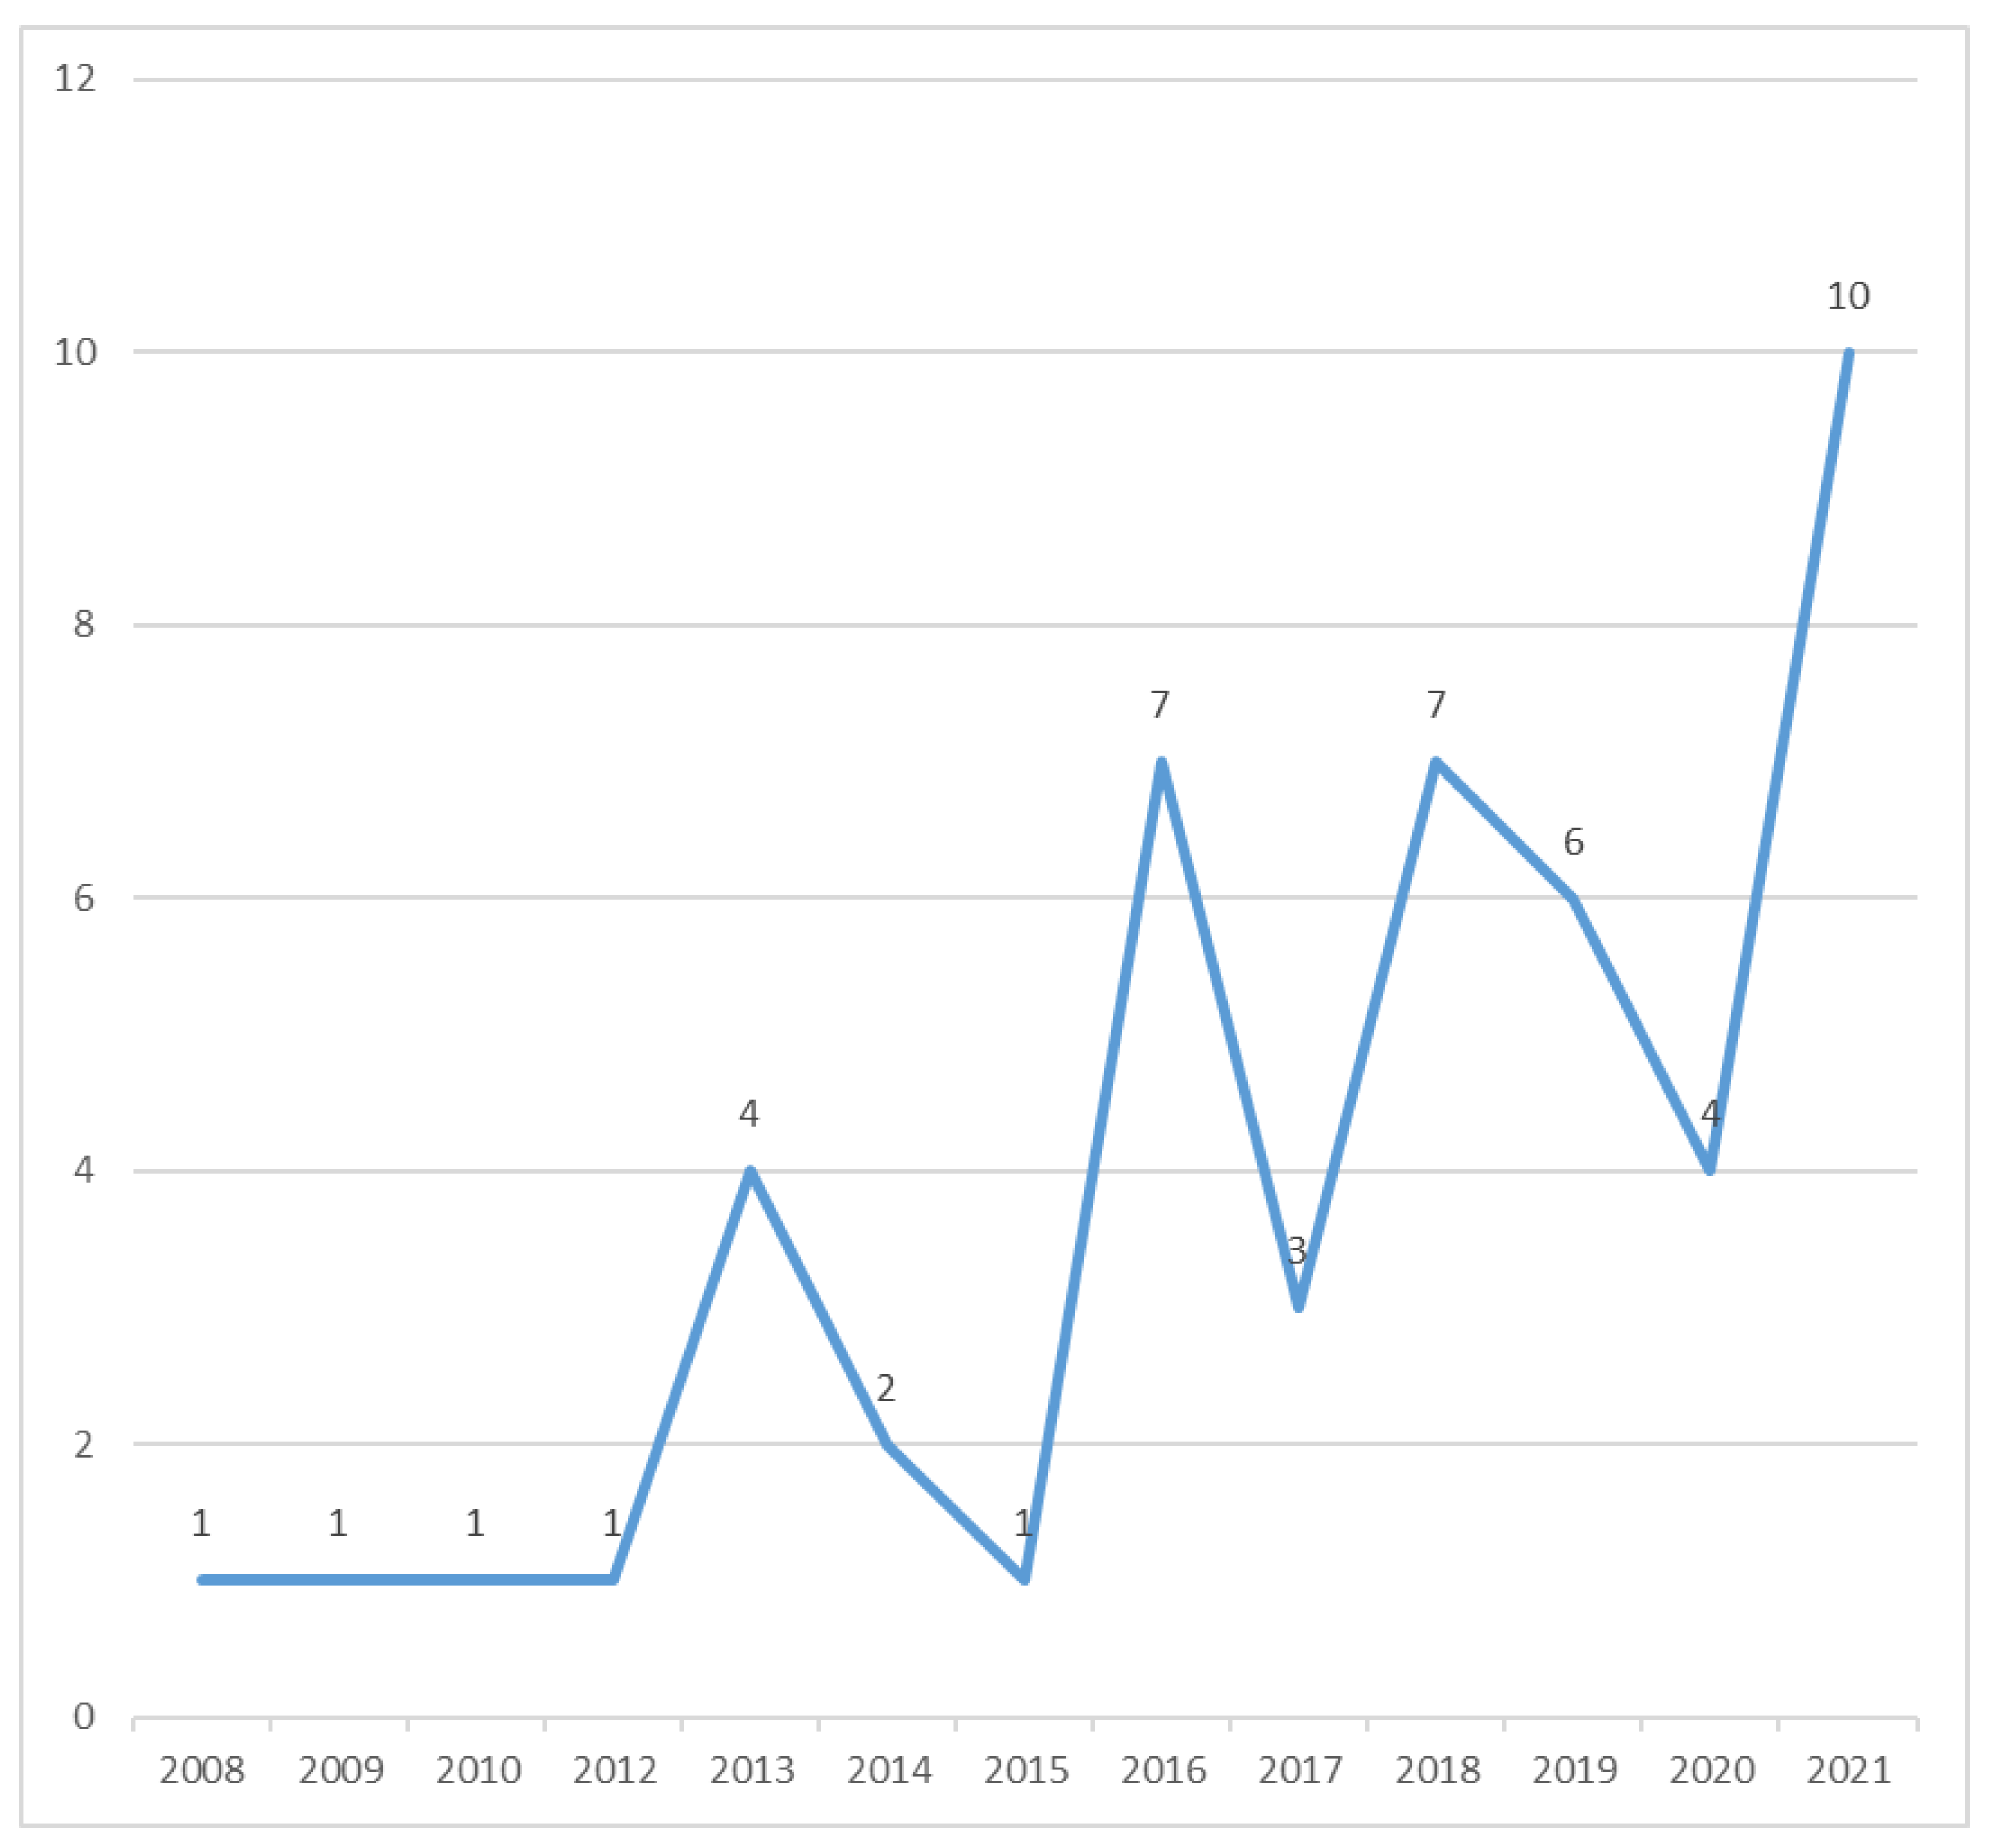
Figure 1. Trends in the annual number of cases of diabetes.
Preprints 147693 g001
Figure 2. Distribution of new cases of diabetes by age groups.
Preprints 147693 g002
Figure 3. HbA1c median values.
Preprints 147693 g003
Figure 4. Percentage of cases by HbA1c level.
Preprints 147693 g004
Figure 5. HbA1c level and parental level education.
Preprints 147693 g005
Figure 6. HbA1c levels and single-parent families.
Preprints 147693 g006
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.