

Submitted:
17 November 2025
Posted:
18 November 2025
You are already at the latest version
Abstract
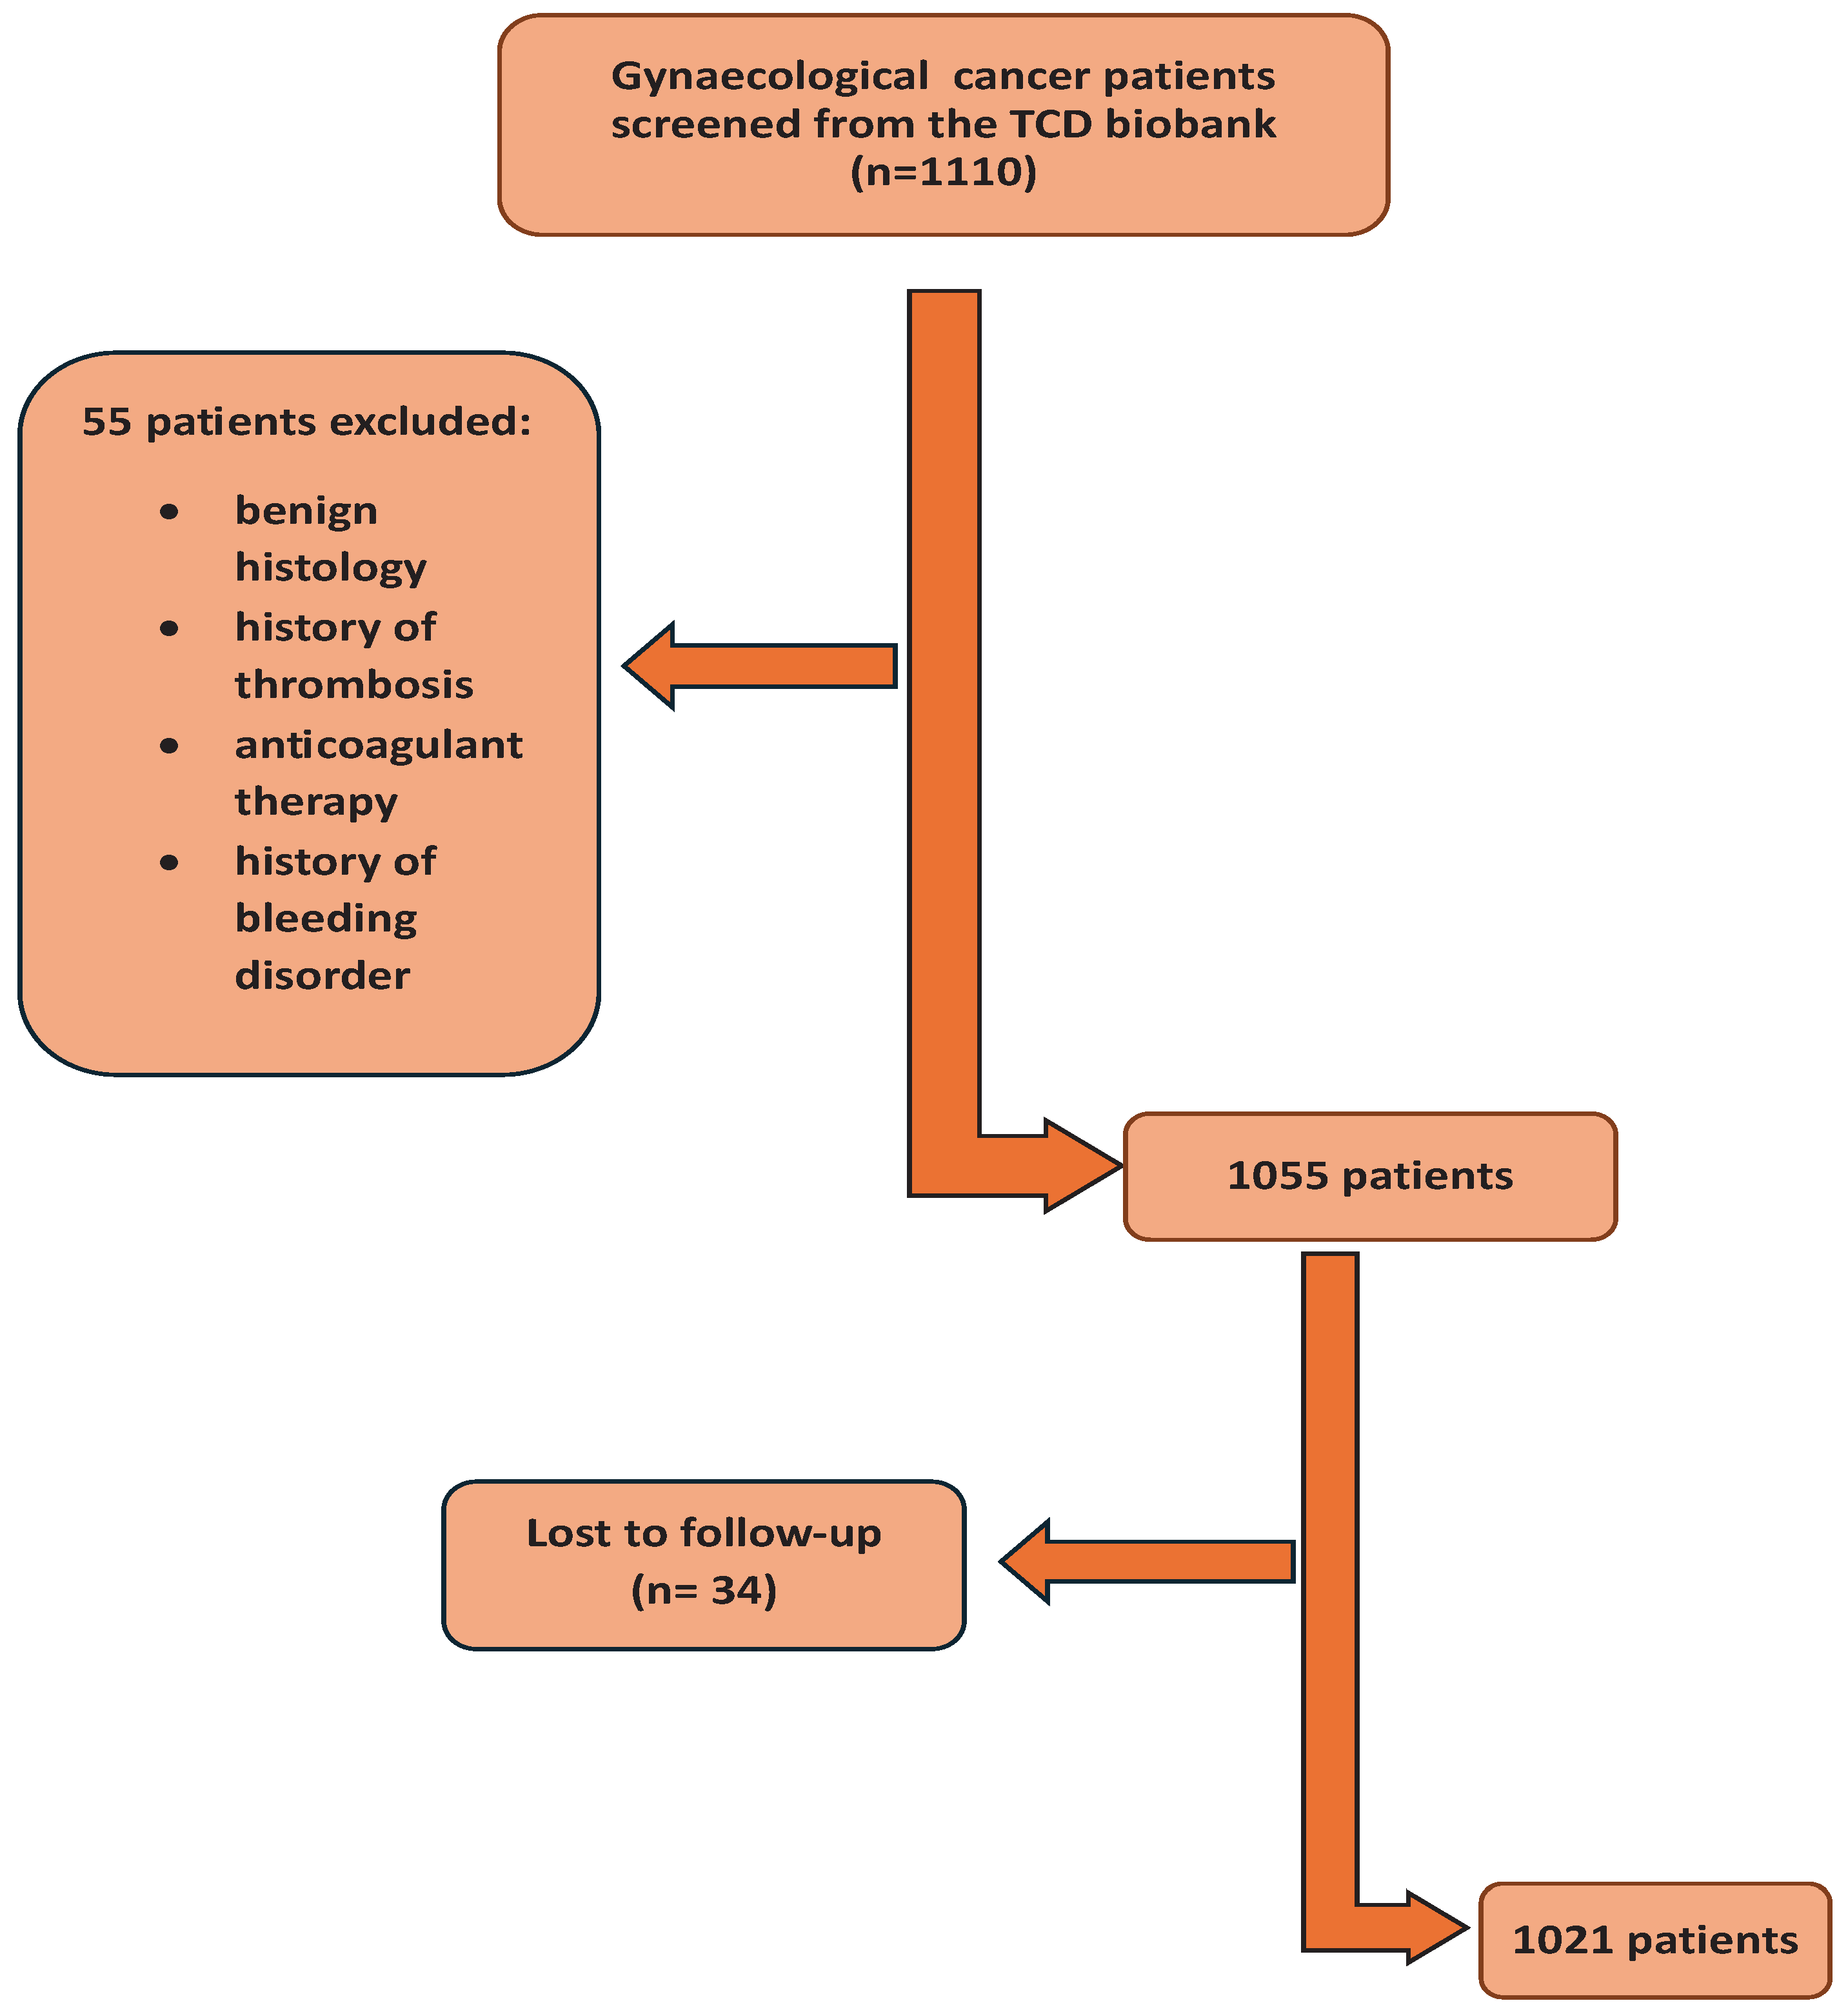
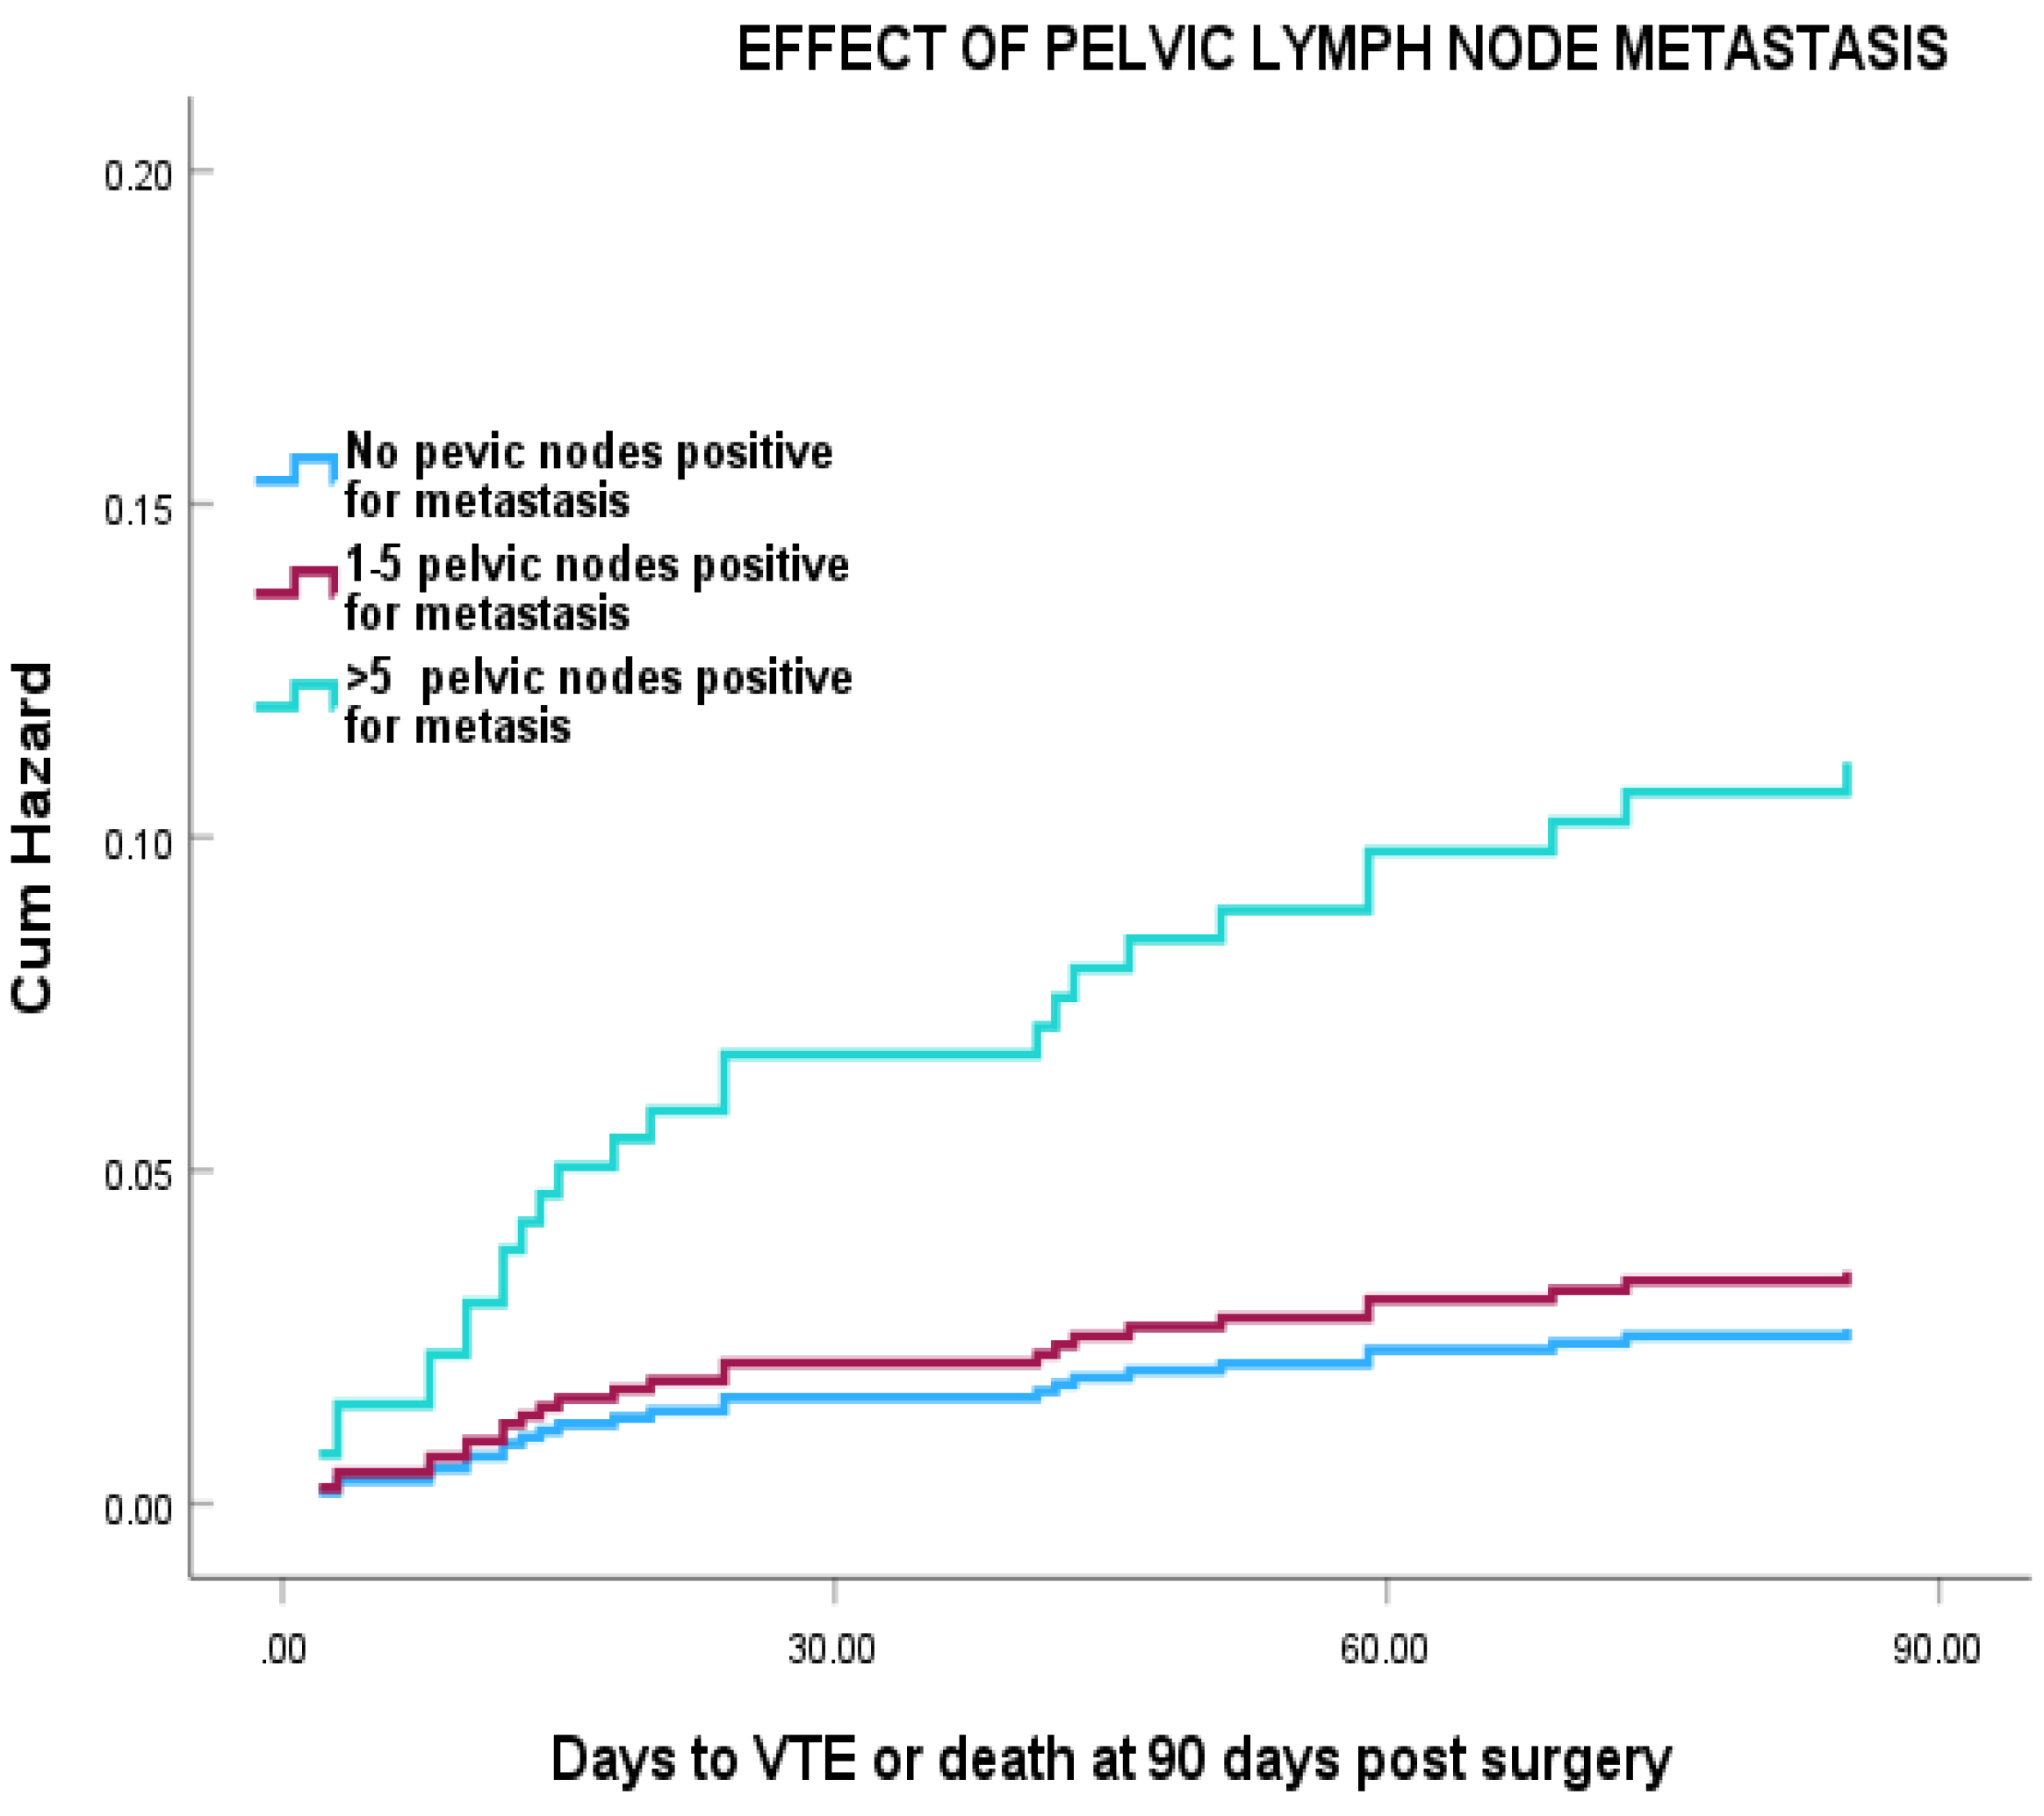
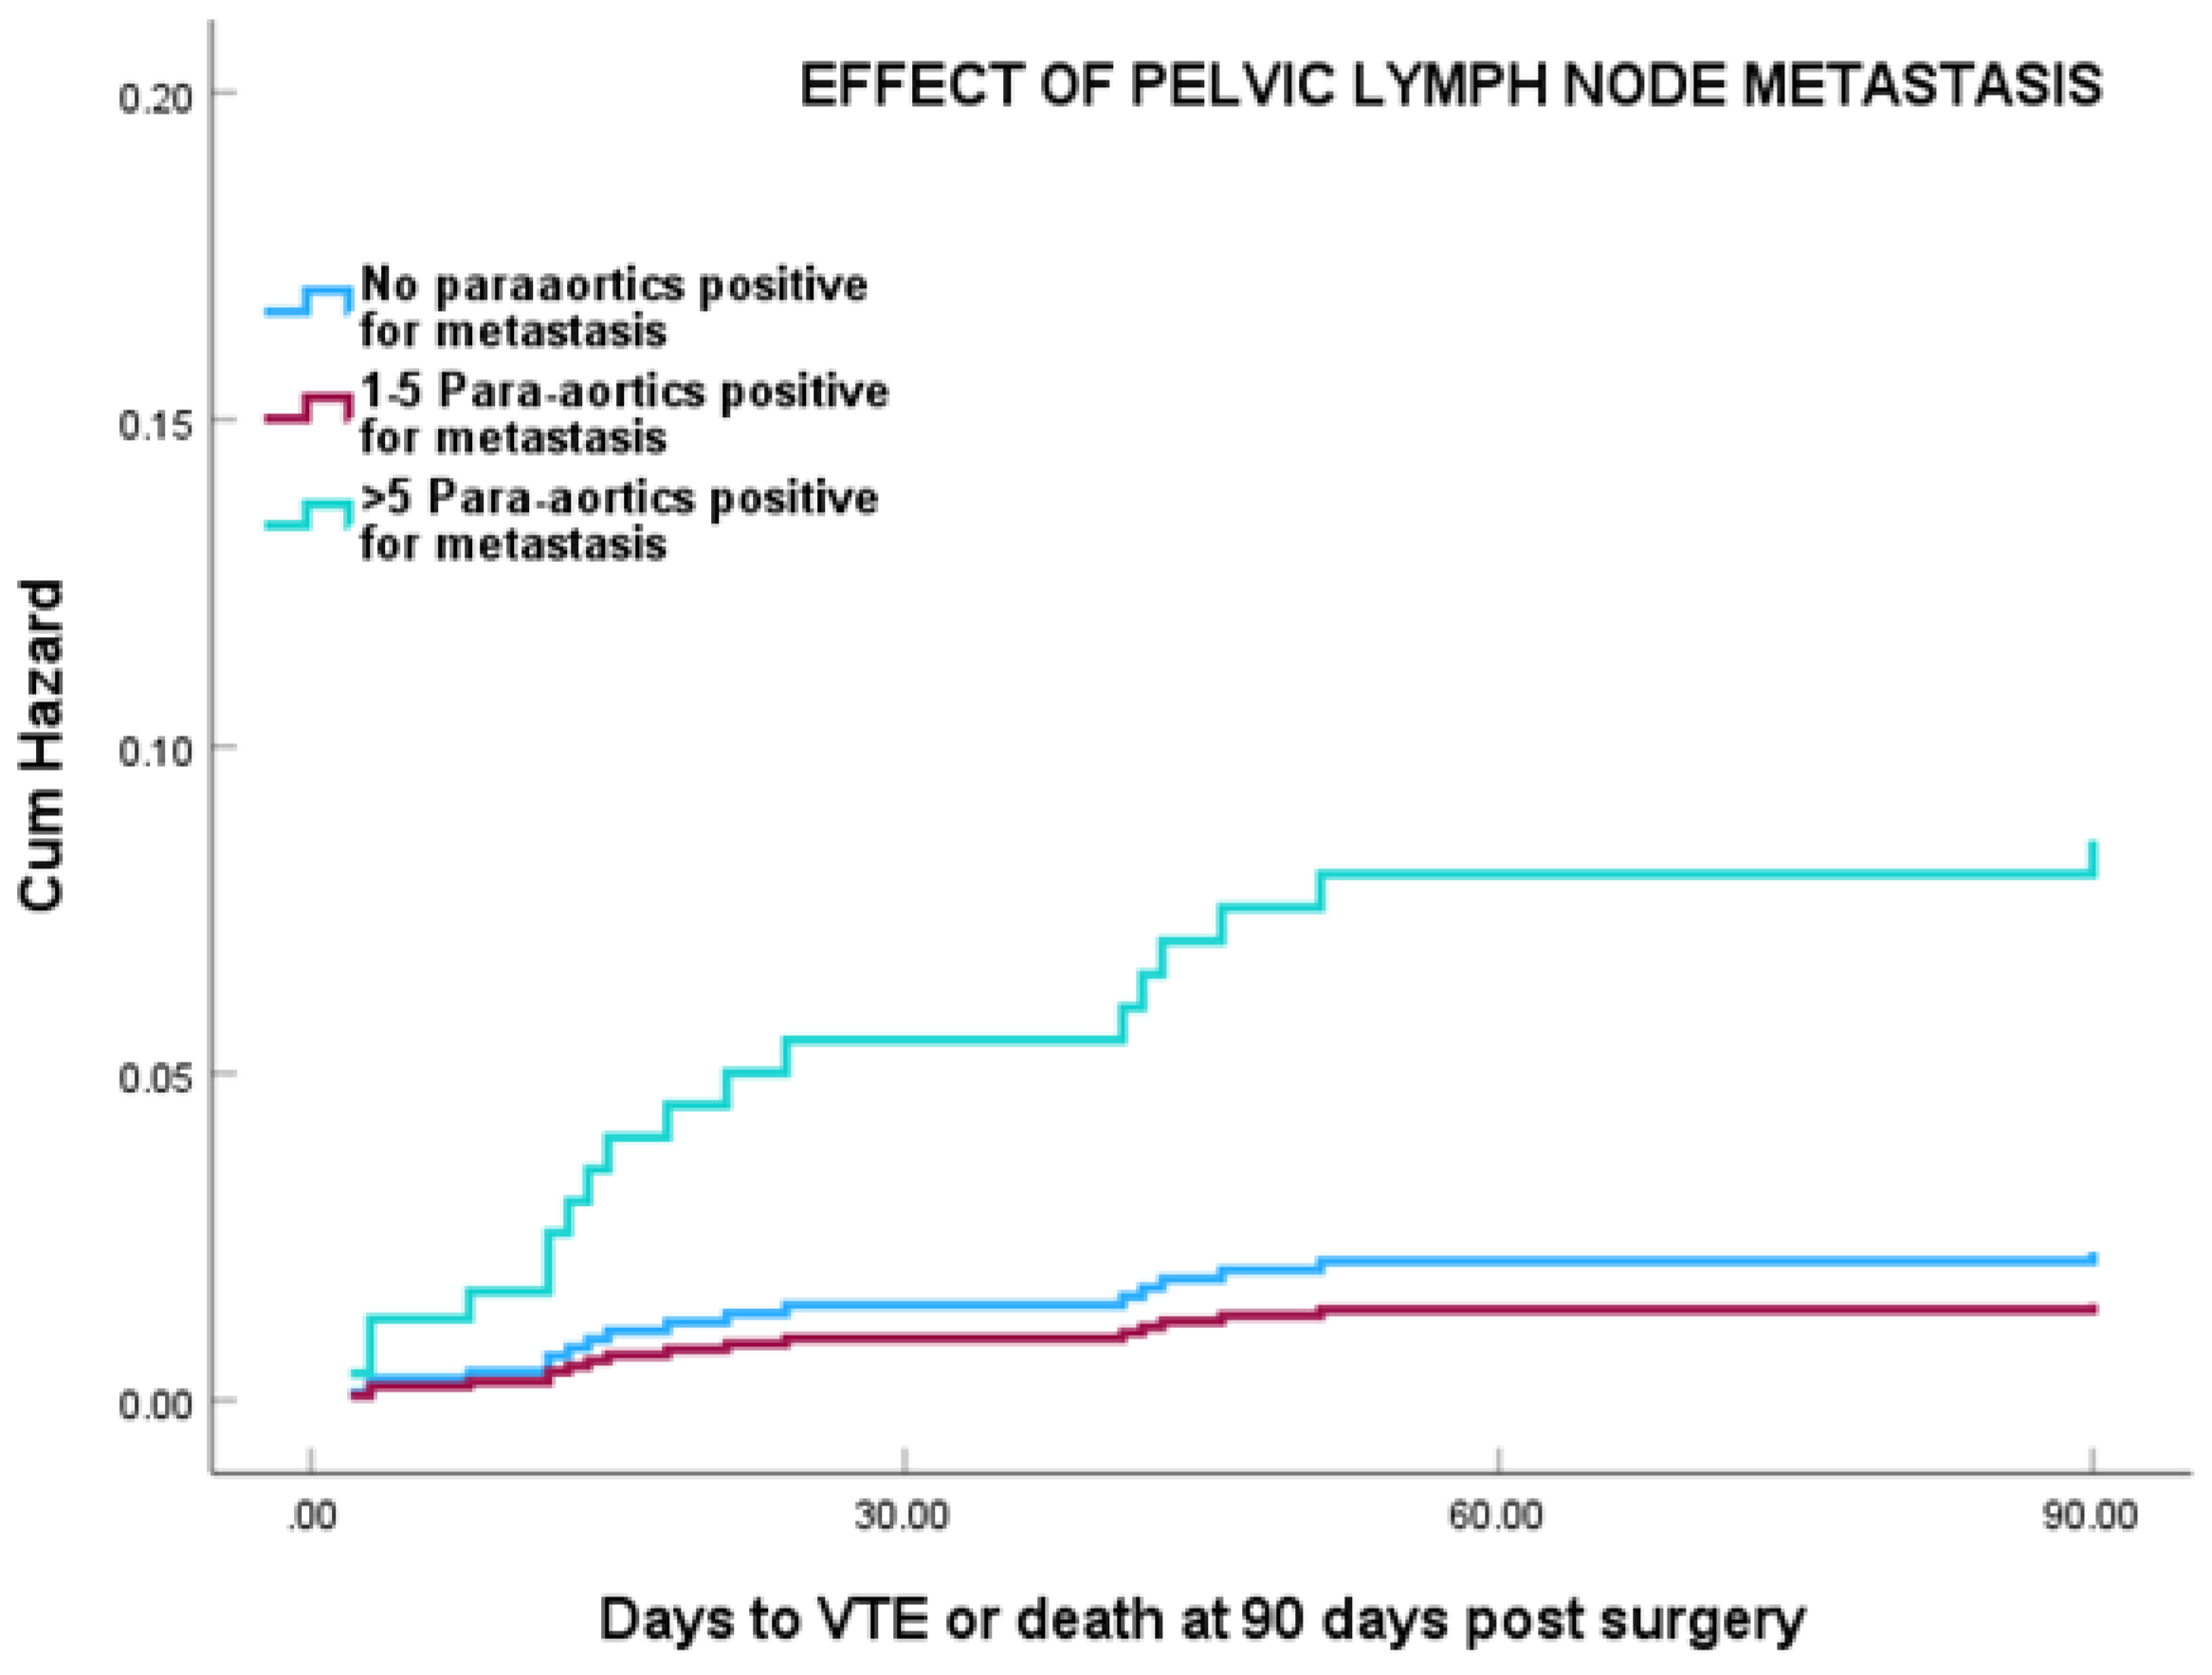
Objective, We investigated the relationship between venous thromboembolism (VTE) and pelvic and para-aortic lymphadenectomy (LND) within the first 90 days post gynaecological cancer surgery. Methods, A retrospective cohort analysis was conducted on 1,021 patients who underwent gynecological cancer surgery between 2006 and 2019. Univariate and multivariate analysis was performed to assess the effects of LND and lymph node (LN) metastasis on VTE occurrence within 90 days post-surgery. Results, 41 patients developed VTE within 90 days post-surgery. Para-aortic LND, was significantly associated with VTE (P < 0.001), with the highest rates (14.6%) observed in patients who had >10 para-aortic LN removed. In patients with pelvic LN metastasis, 10 (7.5%) developed VTE; patients with > 5 pelvic nodes positive for metastasis had a HR =4.83 (95% CI: 0.99- 13.9) after adjustment for age, duration of hospital stay, and surgical approach. The highest VTE rates (27.3%) occurred in patients with >5 para-aortic LN positive for metastasis, HR=3.79 (95% CI 1.44-14.23) after adjustment for age, duration of hospital stay, and surgical approach (P = 0.011). Conclusion, Para-aortic LND significantly increases VTE risk within the first 90 days post-surgery. The risk is further amplified in cases with metastatic LN and persists even after adjustment for other risk factors for VTE. While extended thromboprophylaxis is standard for all cancer patients, our findings suggest that para-aortic LND—especially with nodal metastases—may help identify those who would benefit most from a more tailored, risk-based prophylaxis approach.
Keywords:
1. Introduction
2. Materials and Methods
3. Results
4. Discussion
5. Conclusions
References
- Fernandes CJ, Morinaga LT, Alves Jr JL, Castro MA, Calderaro D, Jardim CV, et al. Cancer-associated thrombosis: the when, how and why. European Respiratory Review. 2019;28(151).
- Abu Saadeh, F.; Norris, L.; O’tOole, S.; Gleeson, N. Venous thromboembolism in ovarian cancer: incidence, risk factors and impact on survival. Eur. J. Obstet. Gynecol. Reprod. Biol. 2013, 170, 214–218. [CrossRef]
- Barbera L, Thomas G. Venous thromboembolism in cervical cancer. Lancet Oncol. 2008;9(1):54-60.
- Pin, S.; Mateshaytis, J.; Ghosh, S.; Batuyong, E.; Easaw, J. Risk Factors for Venous Thromboembolism in Endometrial Cancer. Curr. Oncol. 2020, 27, 198–203. [CrossRef]
- Peedicayil, A.; Weaver, A.; Li, X.; Carey, E.; Cliby, W.; Mariani, A. Incidence and timing of venous thromboembolism after surgery for gynecological cancer. Gynecol. Oncol. 2011, 121, 64–69. [CrossRef]
- Falanga, A.; Ay, C.; Di Nisio, M.; Gerotziafas, G.; Jara-Palomares, L.; Langer, F.; Lecumberri, R.; Mandala, M.; Maraveyas, A.; Pabinger, I.; et al. Venous thromboembolism in cancer patients: ESMO Clinical Practice Guideline. Ann. Oncol. 2023, 34, 452–467. [CrossRef]
- Guo Q, Huang B, Zhao J, Ma Y, Yuan D, Yang Y, et al. Perioperative pharmacological thromboprophylaxis in patients with cancer: a systematic review and meta-analysis. Annals of surgery. 2017;265(6):1087-93.
- Bouchard-Fortier, G.; Geerts, W.H.; Covens, A.; Vicus, D.; Kupets, R.; Gien, L.T. Is venous thromboprophylaxis necessary in patients undergoing minimally invasive surgery for a gynecologic malignancy?. Gynecol. Oncol. 2014, 134, 228–232. [CrossRef]
- Kim, J.S.; Mills, K.A.; Fehniger, J.; Liao, C.; Hurteau, J.A.; Kirschner, C.V.; Lee, N.K.; Rodriguez, G.C.; Yamada, S.D.; Moore, E.S.D.; et al. Venous Thromboembolism in Patients Receiving Extended Pharmacologic Prophylaxis After Robotic Surgery for Endometrial Cancer. Int. J. Gynecol. Cancer 2017, 27, 1774–1782. [CrossRef]
- Kahr, H.S.; Christiansen, O.B.; Høgdall, C.; Grove, A.; Mortensen, R.N.; Torp-Pedersen, C.; Knudsen, A.; Thorlacius-Ussing, O. Endometrial cancer does not increase the 30-day risk of venous thromboembolism following hysterectomy compared to benign disease. A Danish National Cohort Study. Gynecol. Oncol. 2019, 155, 112–118. [CrossRef]
- Concin, N.; Matias-Guiu, X.; Vergote, I.; Cibula, D.; Mirza, M.R.; Marnitz, S.; Ledermann, J.; Bosse, T.; Chargari, C.; Fagotti, A.; et al. ESGO/ESTRO/ESP guidelines for the management of patients with endometrial carcinoma. Int. J. Gynecol. Cancer 2021, 31, 12–39. [CrossRef]
- Chiyoda, T.; Sakurai, M.; Satoh, T.; Nagase, S.; Mikami, M.; Katabuchi, H.; Aoki, D. Lymphadenectomy for primary ovarian cancer: a systematic review and meta-analysis. J. Gynecol. Oncol. 2020, 31, e67. [CrossRef]
- Tzanis, A.A.; Antoniou, S.A.; Zacharoulis, D.; Ntafopoulos, K.; Tsouvali, H.; Daponte, A. The role of systematic pelvic and para-aortic lymphadenectomy in the management of patients with advanced epithelial ovarian, tubal, and peritoneal cancer: A systematic review and meta-analysis. Eur. J. Obstet. Gynecol. Reprod. Biol. 2023, 285, 198–203. [CrossRef]
- Harter, P.; Sehouli, J.; Lorusso, D.; Reuss, A.; Vergote, I.; Marth, C.; Kim, J.W.; Raspagliesi, F.; Lampe, B.; Landoni, F.; et al. LION: Lymphadenectomy in ovarian neoplasms—A prospective randomized AGO study group led gynecologic cancer intergroup trial. J. Clin. Oncol. 2017, 35, 5500. [CrossRef]
- Oonk, M.H.; Planchamp, F.; Baldwin, P.; Bidzinski, M.; Brännström, M.; Landoni, F.; Mahner, S.; Mahantshetty, U.; Mirza, M.; Petersen, C.; et al. European Society of Gynaecological Oncology Guidelines for the Management of Patients With Vulvar Cancer. Int. J. Gynecol. Cancer 2017, 27, 832–837. [CrossRef]
- van Es, N.; Di Nisio, M.; Cesarman, G.; Kleinjan, A.; Otten, H.M.; Mahé, I.; Wilts, I.T.; Twint, D.C.; Porreca, E.; Arrieta, O.; et al. Comparison of risk prediction scores for venous thromboembolism in cancer patients: A prospective cohort study. Haematologica 2017, 102, 1494–1501. [CrossRef]
- Chen, E.C.; Papa, N.; Lawrentschuk, N.; Bolton, D.; Sengupta, S. Incidence and risk factors of venous thromboembolism after pelvic uro-oncologic surgery – a single center experience. BJU Int. 2015, 117, 50–53. [CrossRef]
- Latif, N.; Oh, J.; Brensinger, C.; Morgan, M.; Lin, L.L.; Cory, L.; Ko, E.M. Lymphadenectomy is associated with an increased risk of postoperative venous thromboembolism in early stage endometrial cancer. Gynecol. Oncol. 2021, 161, 130–134. [CrossRef]
- Tyritzis, S.I.; Wallerstedt, A.; Steineck, G.; Nyberg, T.; Hugosson, J.; Bjartell, A.; Wilderäng, U.; Thorsteinsdottir, T.; Carlsson, S.; Stranne, J.; et al. Thromboembolic Complications in 3,544 Patients Undergoing Radical Prostatectomy with or without Lymph Node Dissection. J. Urol. 2015, 193, 117–125. [CrossRef]
- Lyman, G.H.; Carrier, M.; Ay, C.; Di Nisio, M.; Hicks, L.K.; Khorana, A.A.; Leavitt, A.D.; Lee, A.Y.Y.; Macbeth, F.; Morgan, R.L.; et al. American Society of Hematology 2021 guidelines for management of venous thromboembolism: prevention and treatment in patients with cancer. Blood Adv. 2021, 5, 927–974. [CrossRef]
- Prat J, Oncology ftFCoG. Staging Classification for Cancer of the Ovary, Fallopian Tube, and Peritoneum: Abridged Republication of Guidelines From the International Federation of Gynecology and Obstetrics (FIGO). Obstetrics & Gynecology. 2015;126(1):171-4.
- Aletti, G.; Dowdy, S.C.; Podratz, K.C.; Cliby, W.A. Relationship among surgical complexity, short-term morbidity, and overall survival in primary surgery for advanced ovarian cancer. Am. J. Obstet. Gynecol. 2007, 197, 676.e1–676.e7. [CrossRef]
- Kumar, D.R.; Hanlin, E.; Glurich, I.; Mazza, J.J.; Yale, S.H. Virchow's Contribution to the Understanding of Thrombosis and Cellular Biology. Clin. Med. Res. 2010, 8, 168–172. [CrossRef]
- Chai X, Zhu T, Chen Z, Zhang H, Wu X. Improvements and challenges in intraperitoneal laparoscopic para-aortic lymphadenectomy: The novel “tent-pitching” antegrade approach and vascular anatomical variations in the para-aortic region. Acta Obstetricia et Gynecologica Scandinavica. 2024;103(9):1753-63.
- Konno, Y.; Todo, Y.; Minobe, S.; Kato, H.; Okamoto, K.; Sudo, S.; Takeda, M.; Watari, H.; Kaneuchi, M.; Sakuragi, N. A Retrospective Analysis of Postoperative Complications With or Without Para-aortic Lymphadenectomy in Endometrial Cancer. Int. J. Gynecol. Cancer 2011, 21, 385–390. [CrossRef]
- Komatsu, H.; Shimada, M.; Osaku, D.; Deura, I.; Sato, S.; Oishi, T.; Harada, T. Deep vein thrombosis and serum D-dimer after pelvic lymphadenectomy in gynecological cancer. Int. J. Gynecol. Cancer 2020, 30, 860–864. [CrossRef]
- Jiao, Y.; Guo, L.; Wu, L.; Hu, T. Relationship between Hypercoagulable State and Circulating Tumor Cells in Peripheral Blood, Pathological Characteristics, and Prognosis of Lung Cancer Patients. Evidence-Based Complement. Altern. Med. 2021, 2021, 1–5. [CrossRef]
- D'ANdrea, V.; Qian, Z.(.; Yim, K.; Egan, J.; Magnani, C.J.; Feldman, A.; Salari, K.; Tewari, A.; Steele, G.; Mossanen, M.; et al. Anticoagulation prophylaxis patterns following retroperitoneal lymph node dissection for testis cancer. Urol. Oncol. Semin. Orig. Investig. 2023, 41, 489.e1–489.e6. [CrossRef]
- Mahdi, H.; Aljebori, Q.; Lockart, D.; Moulton, L. Risk of Venous Thromboembolism After Laparoscopic Surgery for Gynecologic Malignancy. J. Minim. Invasive Gynecol. 2016, 23, 1057–1062. [CrossRef]
- Ackroyd, S.; Rubin, S.; Houck, K.; Chu, C.; Mantia-Smaldone, G.; Hernandez, E. Lymph node dissection at the time of hysterectomy for uterine cancer is associated with venous thromboembolism: An analysis of the American College of Surgeons National Surgical Quality Improvement Program (NSQIP) database. Gynecol. Oncol. 2020, 159, 326–327. [CrossRef]
- Nguyen, N.; Cronan, M.; Braley, S.; Rivers, R.; Wolfe, B. Duplex ultrasound assessment of femoral venous flow during laparoscopic and open gastric bypass. Surg. Endosc. 2003, 17, 285–290. [CrossRef]
- Abu Saadeh, F.; Marchocki, Z.; O'TOole, S.; Ibrahim, N.; Gleeson, N.; Norris, L. Extended thromboprophylaxis post gynaecological cancer surgery; the effect of weight adjusted and fixed dose LMWH (Tinzaparin). Thromb. Res. 2021, 207, 25–32. [CrossRef]
- Marchocki, Z.; Norris, L.; O'TOole, S.; Gleeson, N.; Abu Saadeh, F. Patients’ experience and compliance with extended low molecular weight heparin prophylaxis post-surgery for gynecological cancer: a prospective observational study. Int. J. Gynecol. Cancer 2019, 29, 802–809. [CrossRef]
- Lee, J.Y.; Oh, I.-Y.; Lee, J.-H.; Kim, S.-Y.; Kwon, S.S.; Yang, H.-J.; Kim, Y.-K.; Bang, S.-M. The increased risk of bleeding due to drug-drug interactions in patients administered direct oral anticoagulants. Thromb. Res. 2020, 195, 243–249. [CrossRef]

| No VTE within 90 days (n=980) | VTE within 90 days( n= 41) | P value | |
| Age (years) median(IQR) | 590 (49-67) | 66 (54-73) | 0.045 |
|
Tumour site: Ovary Endometrium Cervix Other |
461(47.0%) 389(39.6%) 97 (9.8%) 33(3.3%) |
27 (65.8%) 9 (21.9%) 2 (4.8%) 3 (7.3%) |
0.031 |
|
Histology: Clear cell Serous Mucinous Endometrioid (ovarian) Endometrial adenocarcnoma Squamous Sarcoma Mixed Borderline Other |
36 (3.6%) 289(29.4%) 32 (3.2%) 41 (4.1%) 300(30.6%) 69 (7.0%) 12 ( 1.2%) 45 (4.6%) 63 (6.4%) 93(9.4%) |
1(2.4%) 23(56.1%) 0(0%) 1 (2.4%) 6 (14.6%) 2 (4.87%) 0 (0%) 3 (7.3 %) 1 (2.4%) 4 (9.7%) |
0.082 |
|
Stage: I II III IV Recurrent N/A Missing |
511 (52.1%) 74 (7.5%) 244(24.8%) 112(11.4%) 36 (3.6%) 1( 0.1%) 2 ( 0.2%) |
11(26.8%) 2 (4.8%) 18 (43.9%) 8(19.5%) 2 (4.8%) 0 (0%) 0( 0%) |
0.022 |
|
Grade: I II III N/A |
288 (29.3%) 196 (20.0%) 392 (40.0%) 104 (10.6%) |
3 (7.3%) 7 (17.1%) 26(63.4%) 5 (12.1%) |
0.020 |
|
BMI >30 kg/m2 <30 kg/m2 Missing |
362 (37%) 548 (55.9%) 70 (7.1%) |
16(39.0%) 24 (58.5%) 1(2.4%) |
0.97 |
|
Extended prophylaxis Yes No N/A |
747 (76.2%) 229 (23.3%) 4 (0.4%) |
28 (68.3%) 12 (29.2%) 1 (2.4) |
0.341 |
|
Chemotherapy: Neoadjuvant Adjuvant No chemotherapy Missing |
125(12.7%) 332(33.8%) 522(53.2%) 1 ( 0.1%) |
8 (19.5%) 20(48.5%) 13(31.7%) 0 ( 0%) |
0.025 |
|
Radiotherapy: Yes No Missing |
283(28.8%) 694(70.6%) 3(0.3%) |
5(12.1%) 36 (87.8%) 0 (0.0%) |
0.108 |
|
Surgical Low Complexity Intermediate High Missing data |
381 (38.8%) 506(51.6%) 90 (9.1% ) 3 (0.3%) |
11 (26.8%) 15 (36.5%) 15 (36.5%) 0(0.0%) |
<0.001 |
|
Surgical Open Approach Laparoscopic Missing |
589(60.1%) 390 (39.7%) 1 (0.11%) |
33 (80.4%) 8 (19.5%) |
0.009 |
| Duration of hospital stay (median days (IQR)) | 9.8 ( 2 -120) | 20.6 (5-70) | <0.001 |
| History of other cancer | 130 (13.2%) | 9 (23.3%) | 0.115 |
| No VTE within 90 days post-surgery (n) | VTE within 90 days post surgery (n) | Total (n) | P value | |
| No pelvic nodes removed | 264 (95.3%) | 13(4.7%) | 277 | 0.652 |
| 1-5 Pelvic nodes removed | 169 (96.0%) | 7 (4.0%) | 176 | |
| 6-10 Pelvic nodes removed | 192 (97.5%) | 5 (2.5%) | 197 | |
| >10 pelvic lymph node removed | 340 (95.5%) | 16 (4.5%) | 356 |
| No VTE within 90 days post-surgery (n) | VTE within 90 days post surgery (n) | Total | P Value | |
| No para-aortic nodes removed | 531 (95.8%) | 23 (4.2%) | 554 | 0.001 |
| 1-5 para-aortic nodes removed | 296 (97.0%) | 9 (3.0%) | 305 | |
| 6-10 paraaortic nodes removed | 103 (97.2%) | 3 (2.8%) | 106 | |
| >10 paraaortic nodes removed | 35 (85.4%) | 6 (14.6%) | 41 |
| No VTE within 90 days post-surgery (n) | VTE within 90 days post surgery (n) | Total (n) | P Value | |
| Total number of patients with pelvic nodes removed (n) | 701 | 28 | 729 | |
| Negative for metastasis (n) | 580 (97.0) | 18 (3.0) | 598 | 0.000 |
| 1-5 pelvic nodes positive for metastasis | 106 (94.6) | 6 (5.4) | 112 | |
| > 5 pelvic nodes positive for metastasis | 15 (78.9) | 4 (21.1) | 19 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).