

Submitted:
20 August 2025
Posted:
01 September 2025
You are already at the latest version
Abstract
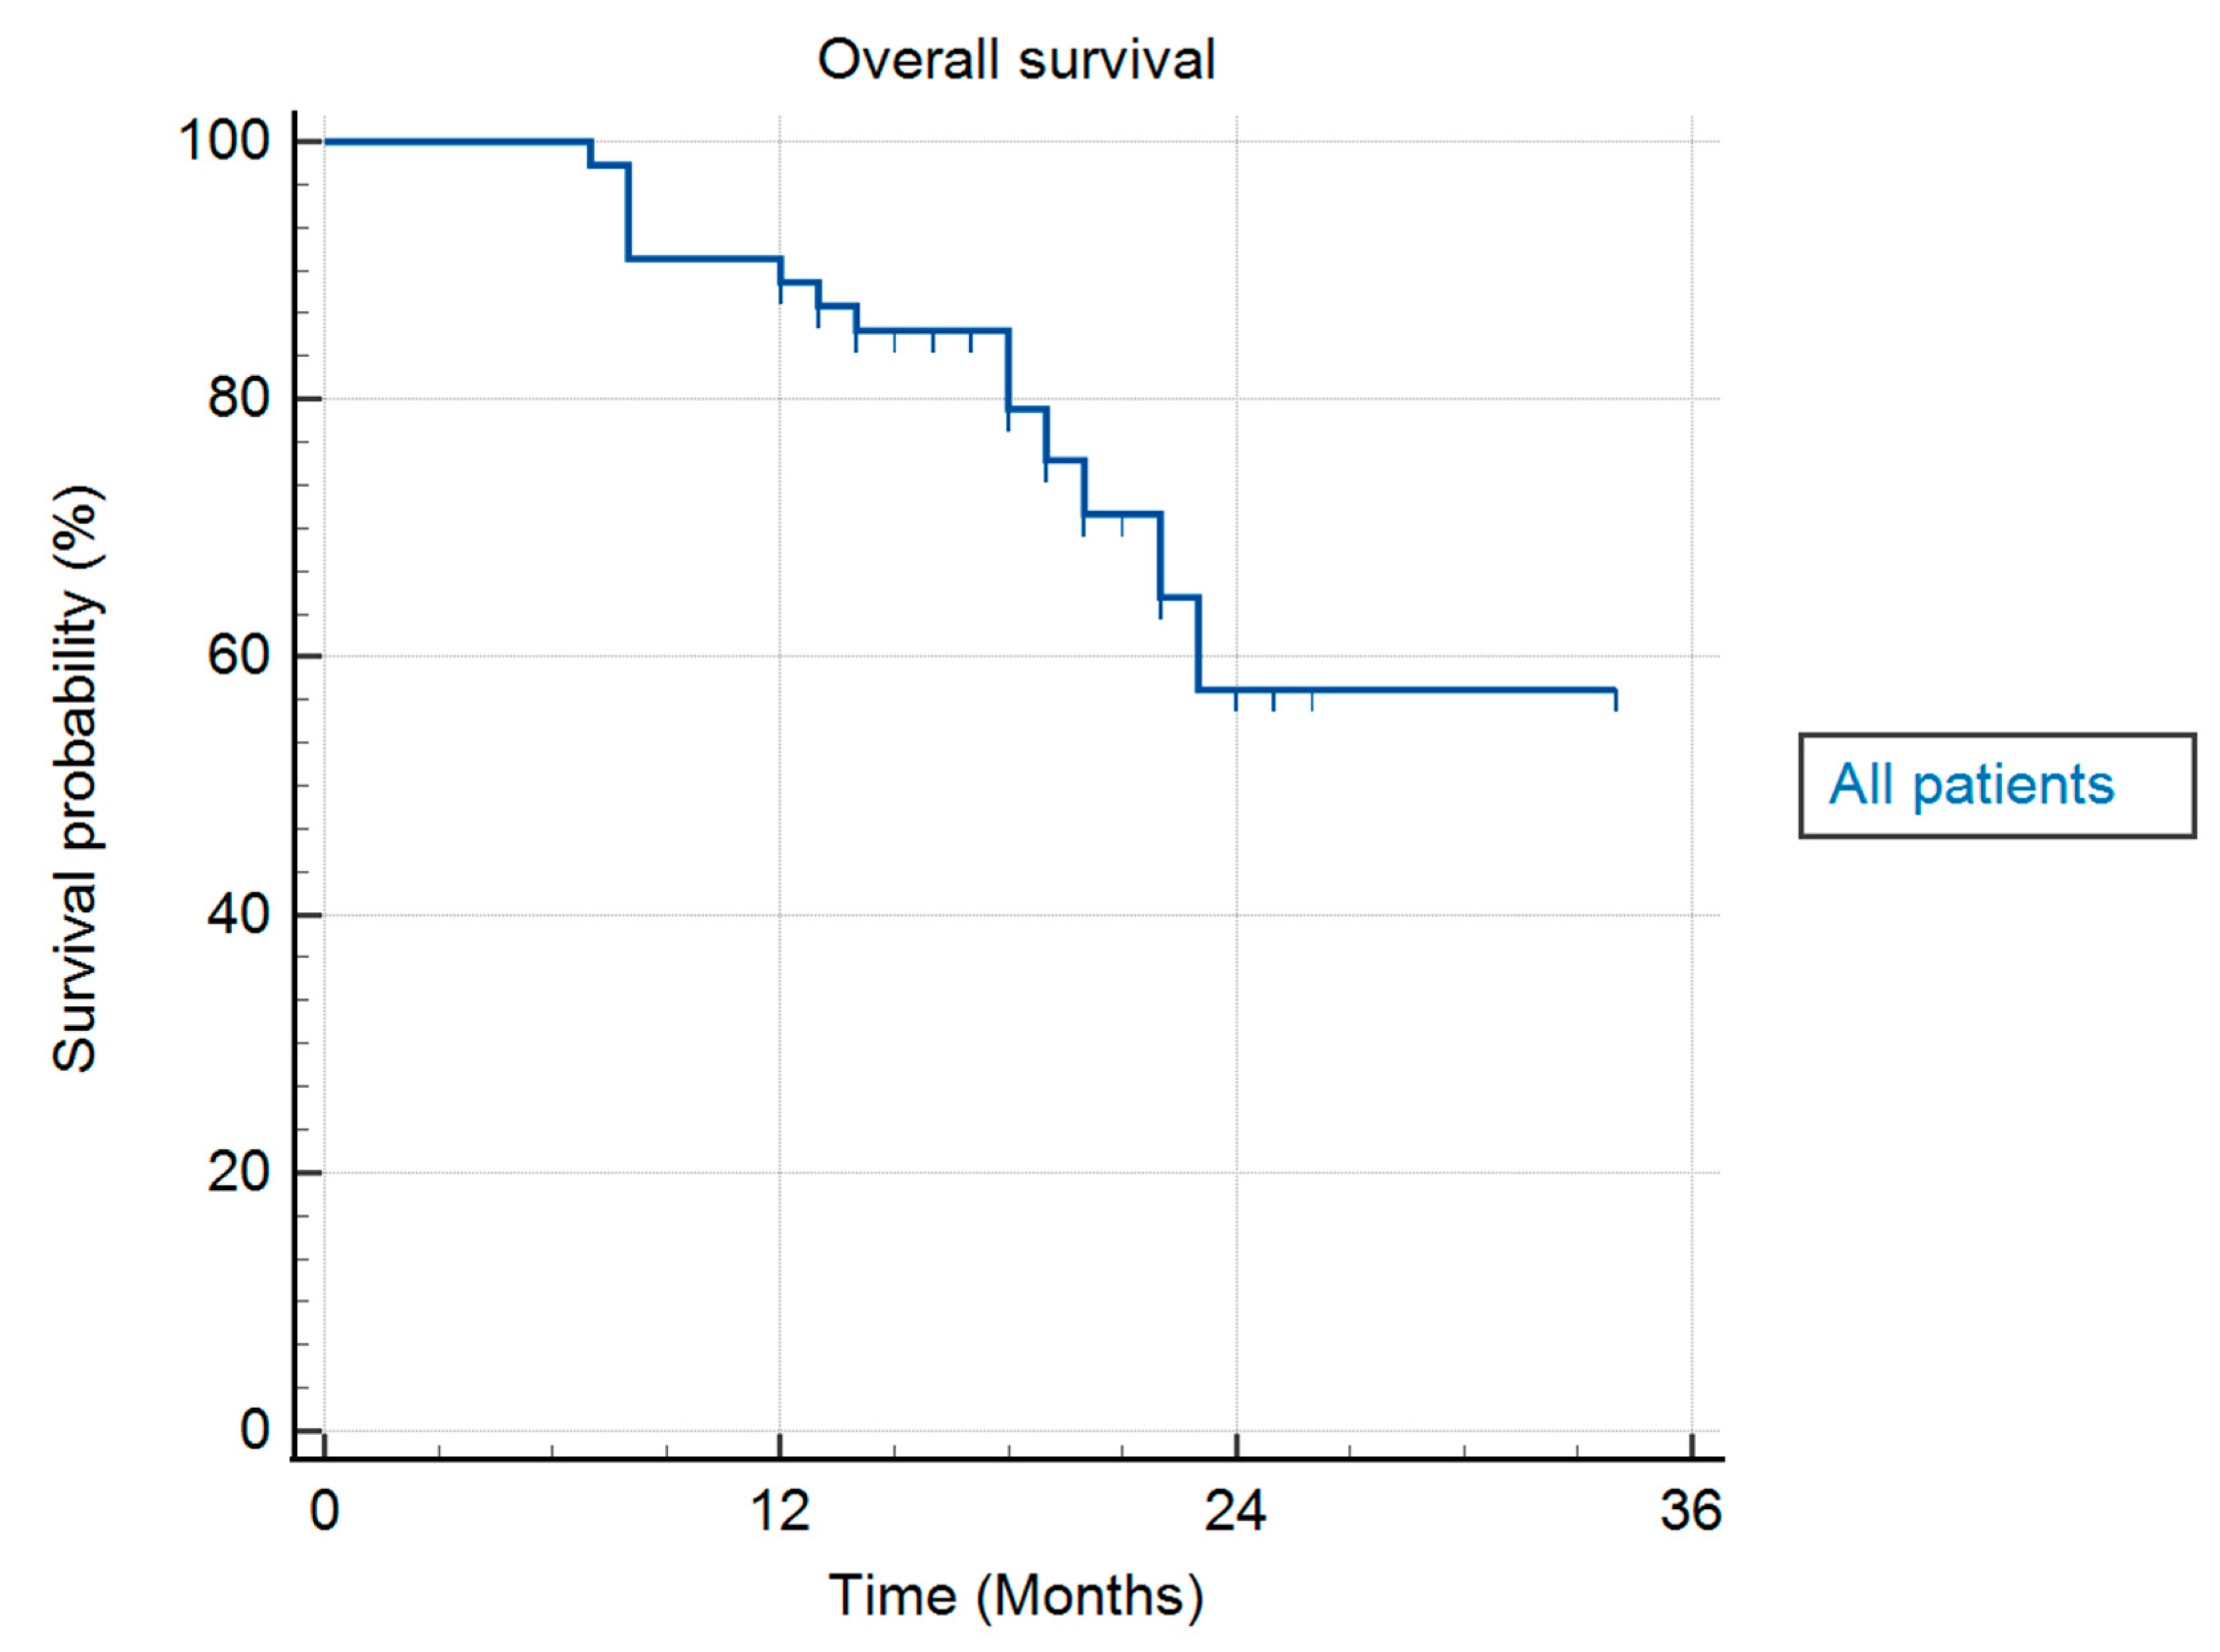
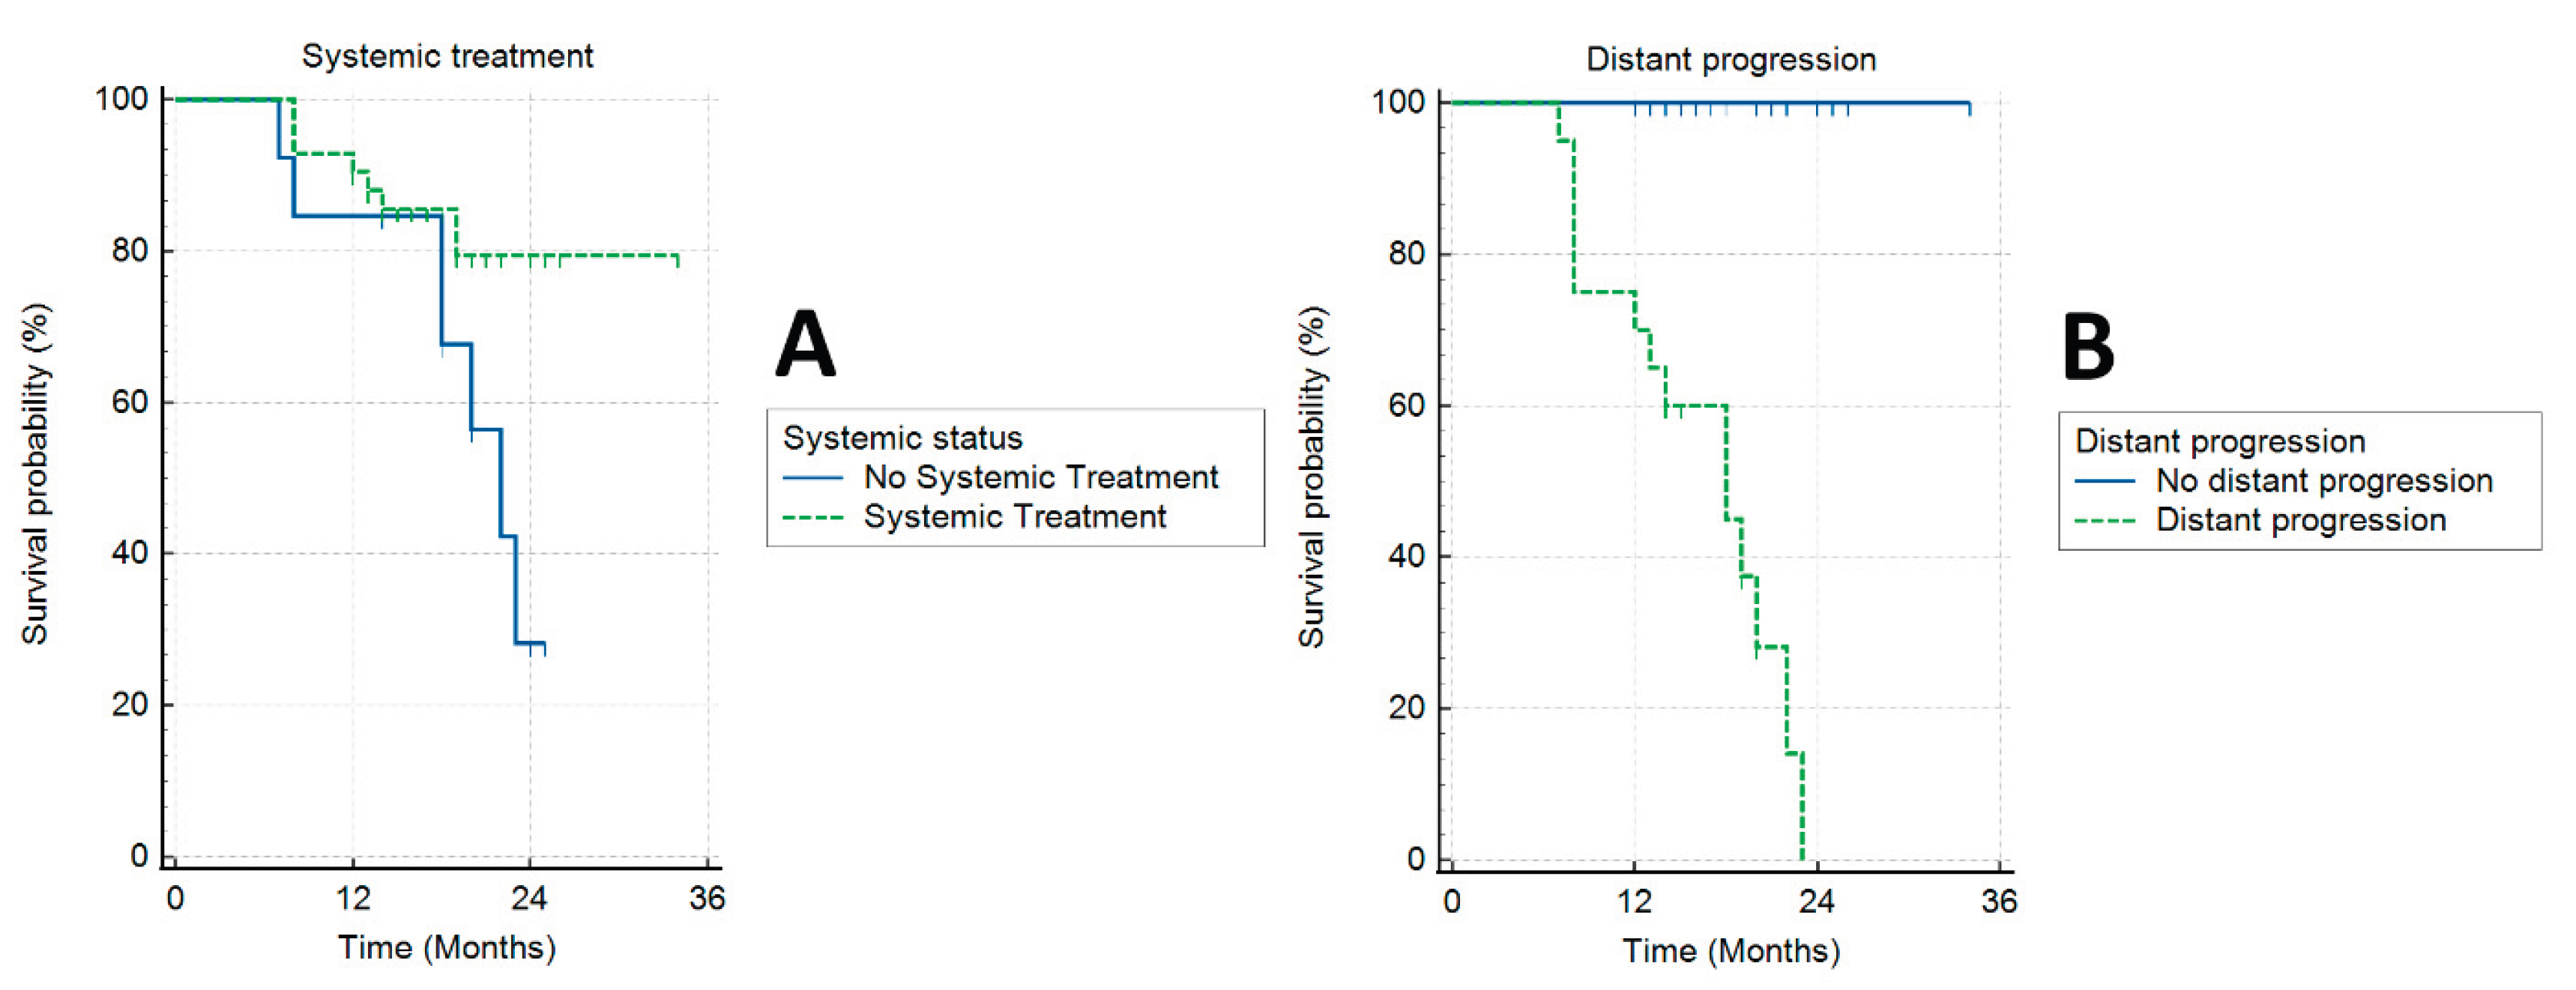
Background: The aim of this study was to present the technique and preliminary results of efficacy and safety for single-fraction SBRT for LAPC using Total Intravenous Anaesthesia and Optical Surface Guidance as motion management. Methods: Fifty-five patients were treated with SBRT in a single-fraction receiving median BED10 = 128.9 Gy. Forty-two patients received systemic treatment. End points were OS, FFLP, PFS, and toxicity. Actuarial survival analysis and univariate analysis were investigated. Results: Median follow-up was 15 months. Mean OS was 26.7 months. One-year FFLP and 1-year OS were 100% and 90.9%, respectively. Median PFS was 18 months, and 1-year PFS was 85.5%. Thirty-five patients (63.6%) were alive at the time of analysis. No acute/late toxicity > G2/G1 was reported. Conclusions: SBRT for LAPC using Total Intravenous Anaesthesia and Optical Surface Guidance presented as an effective and safe treatment with very low toxicity.
Keywords:
1. Introduction
2. Materials and Methods
2.1. Patients
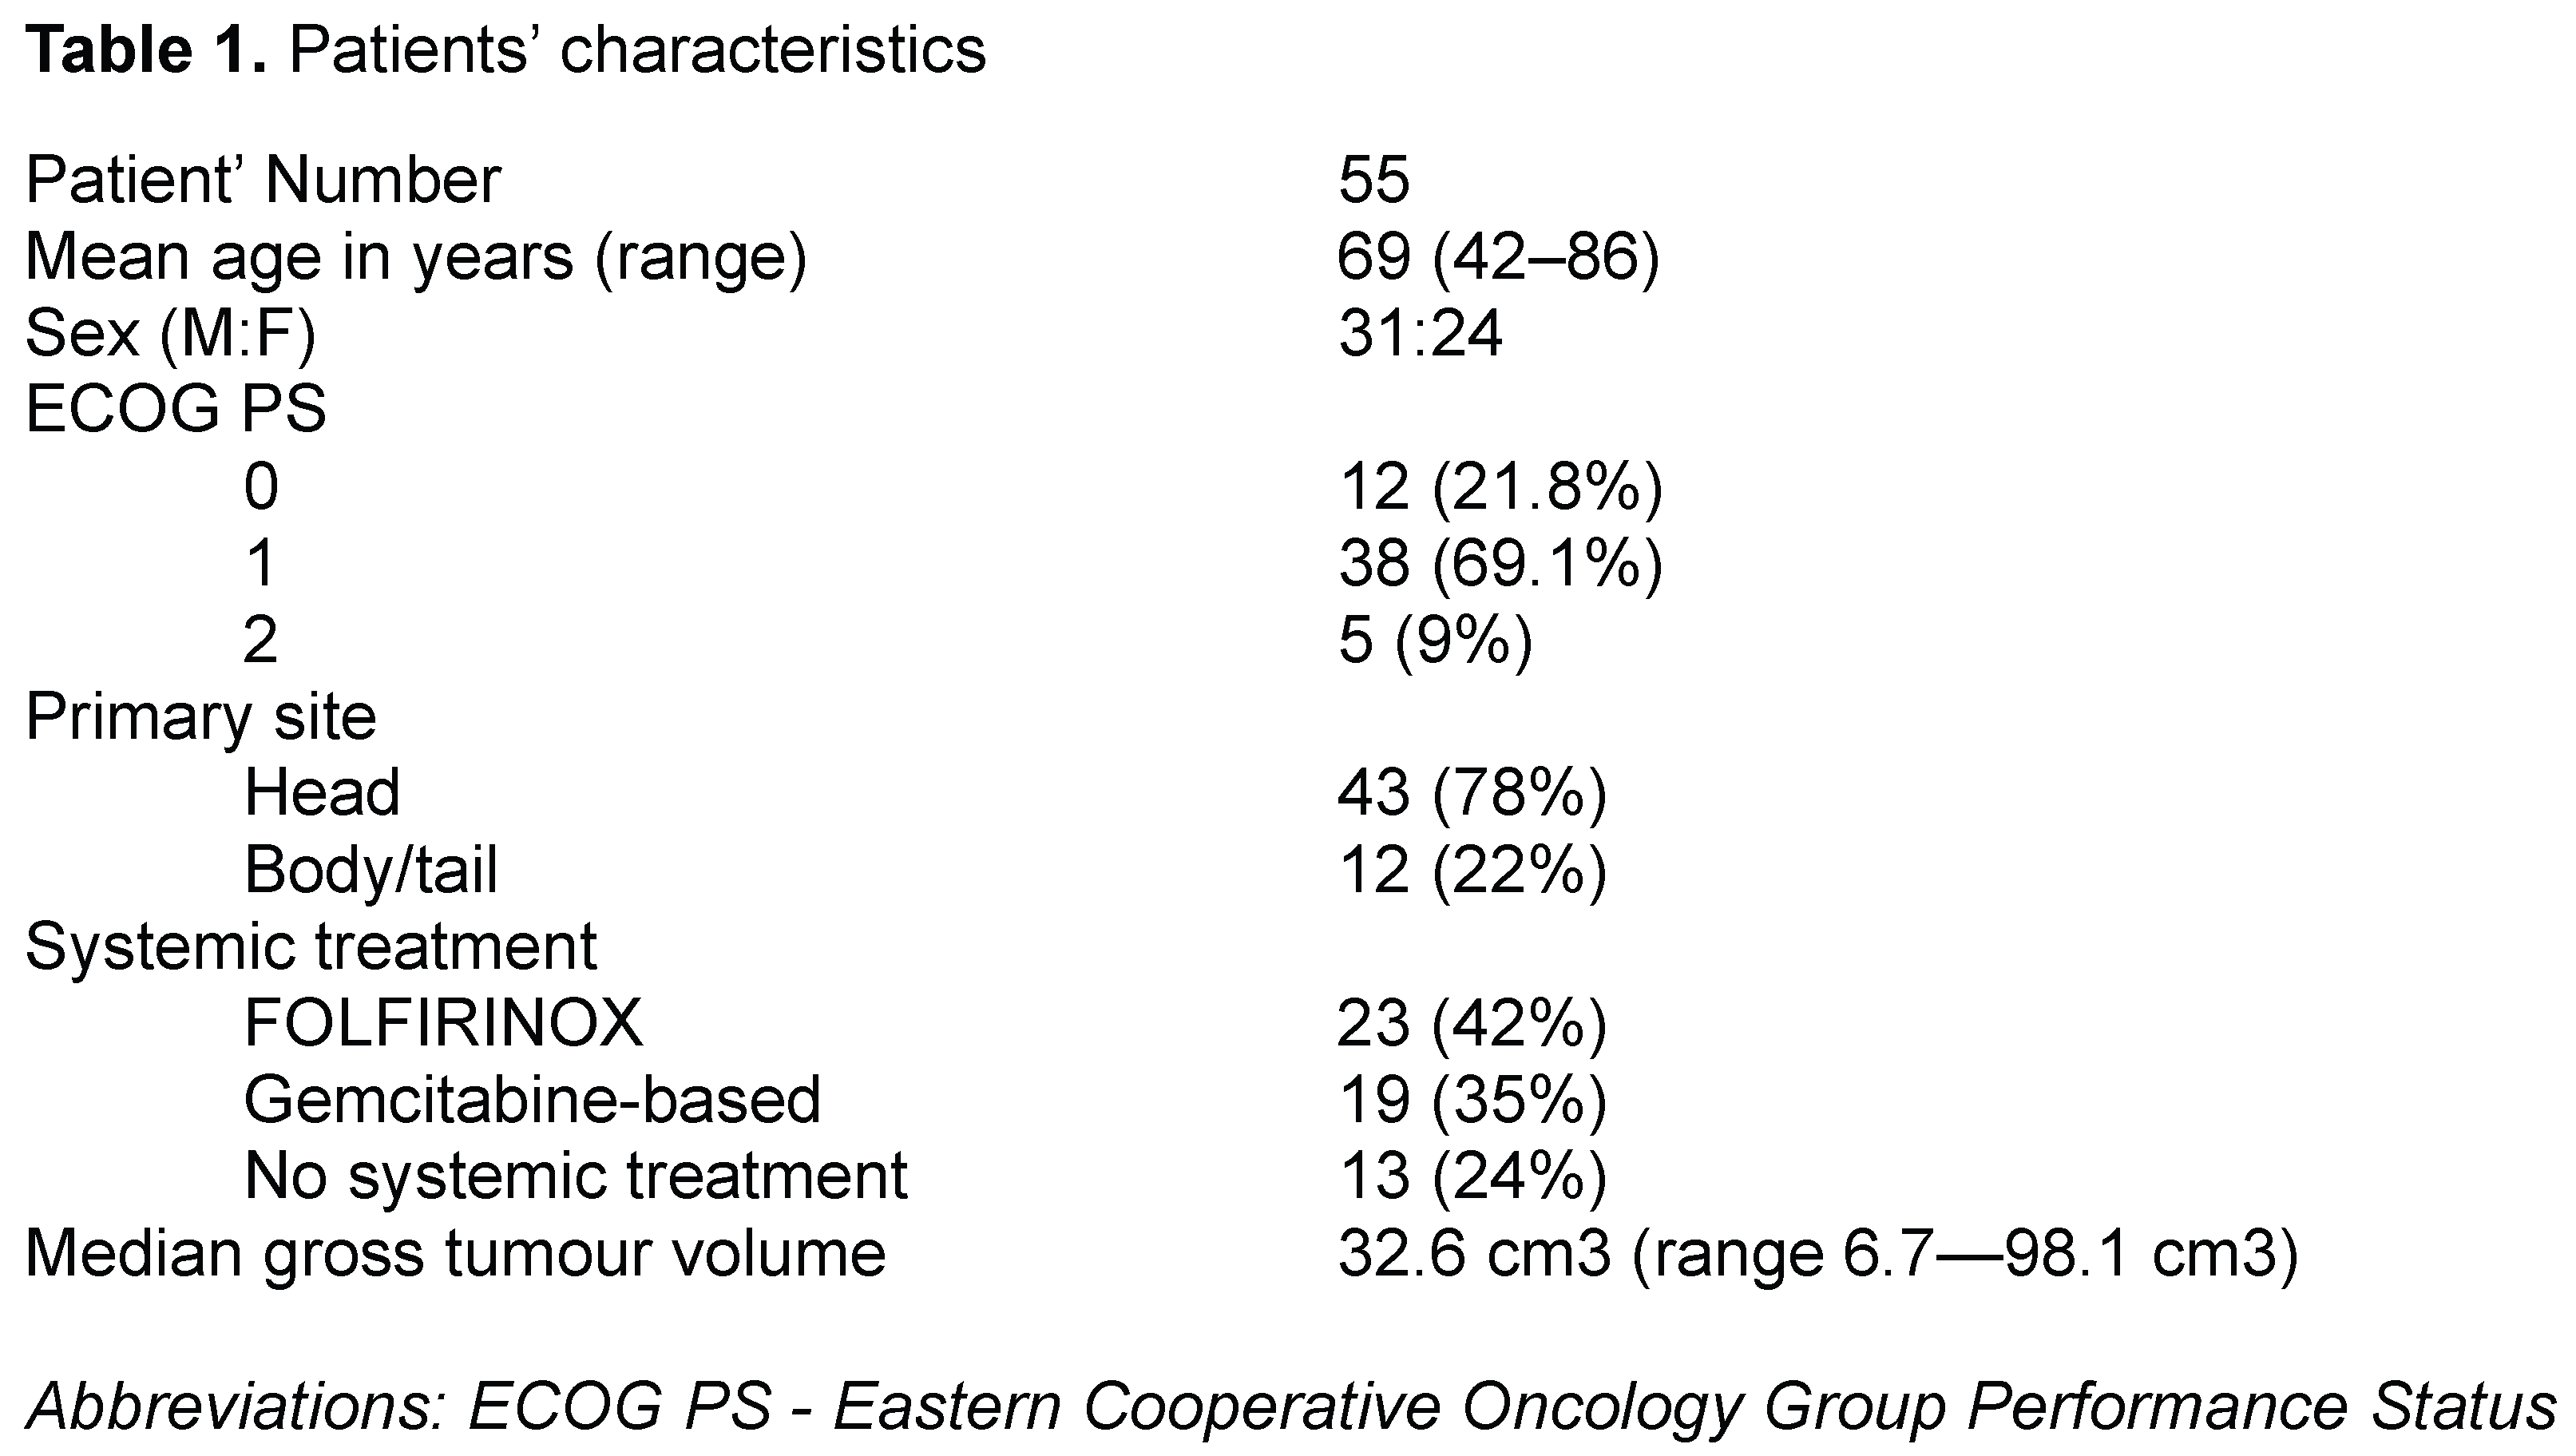
2.2. Patients’ Preparations for the Treatment (Title - Impossible to Revise)
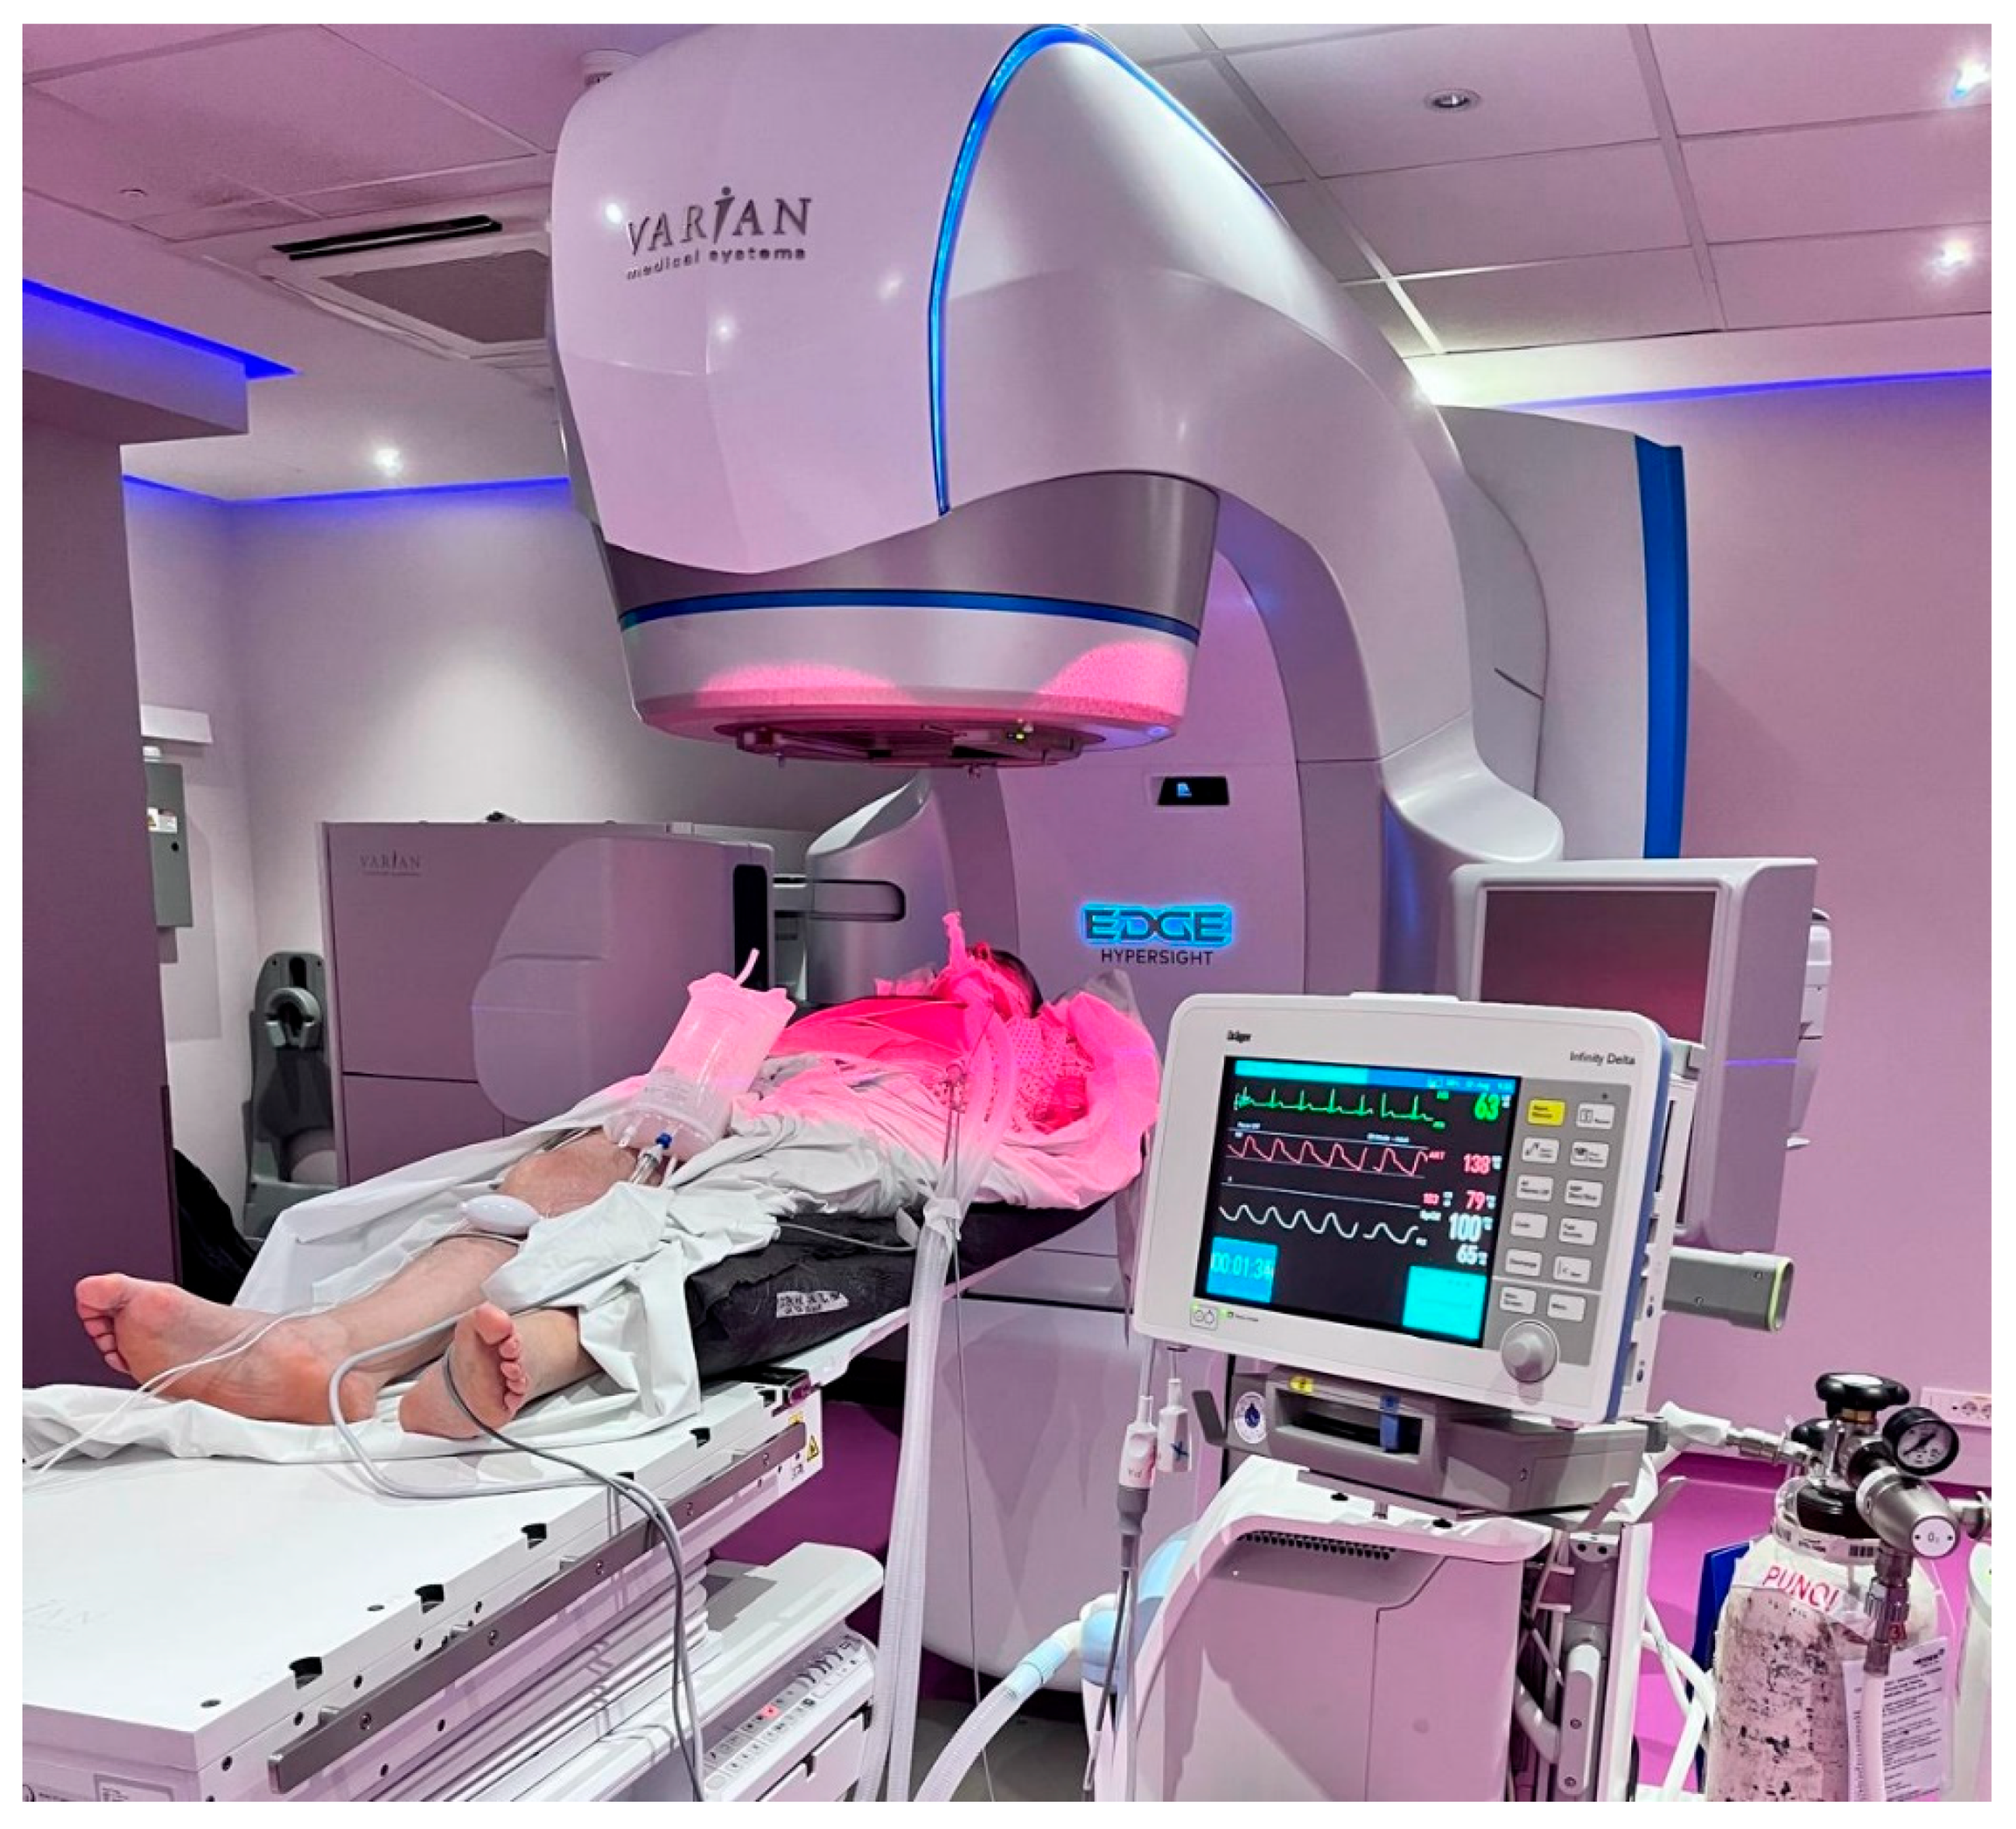
2.3. Total Intravenous Anaesthesia with Assist-Control Mechanical Ventilation
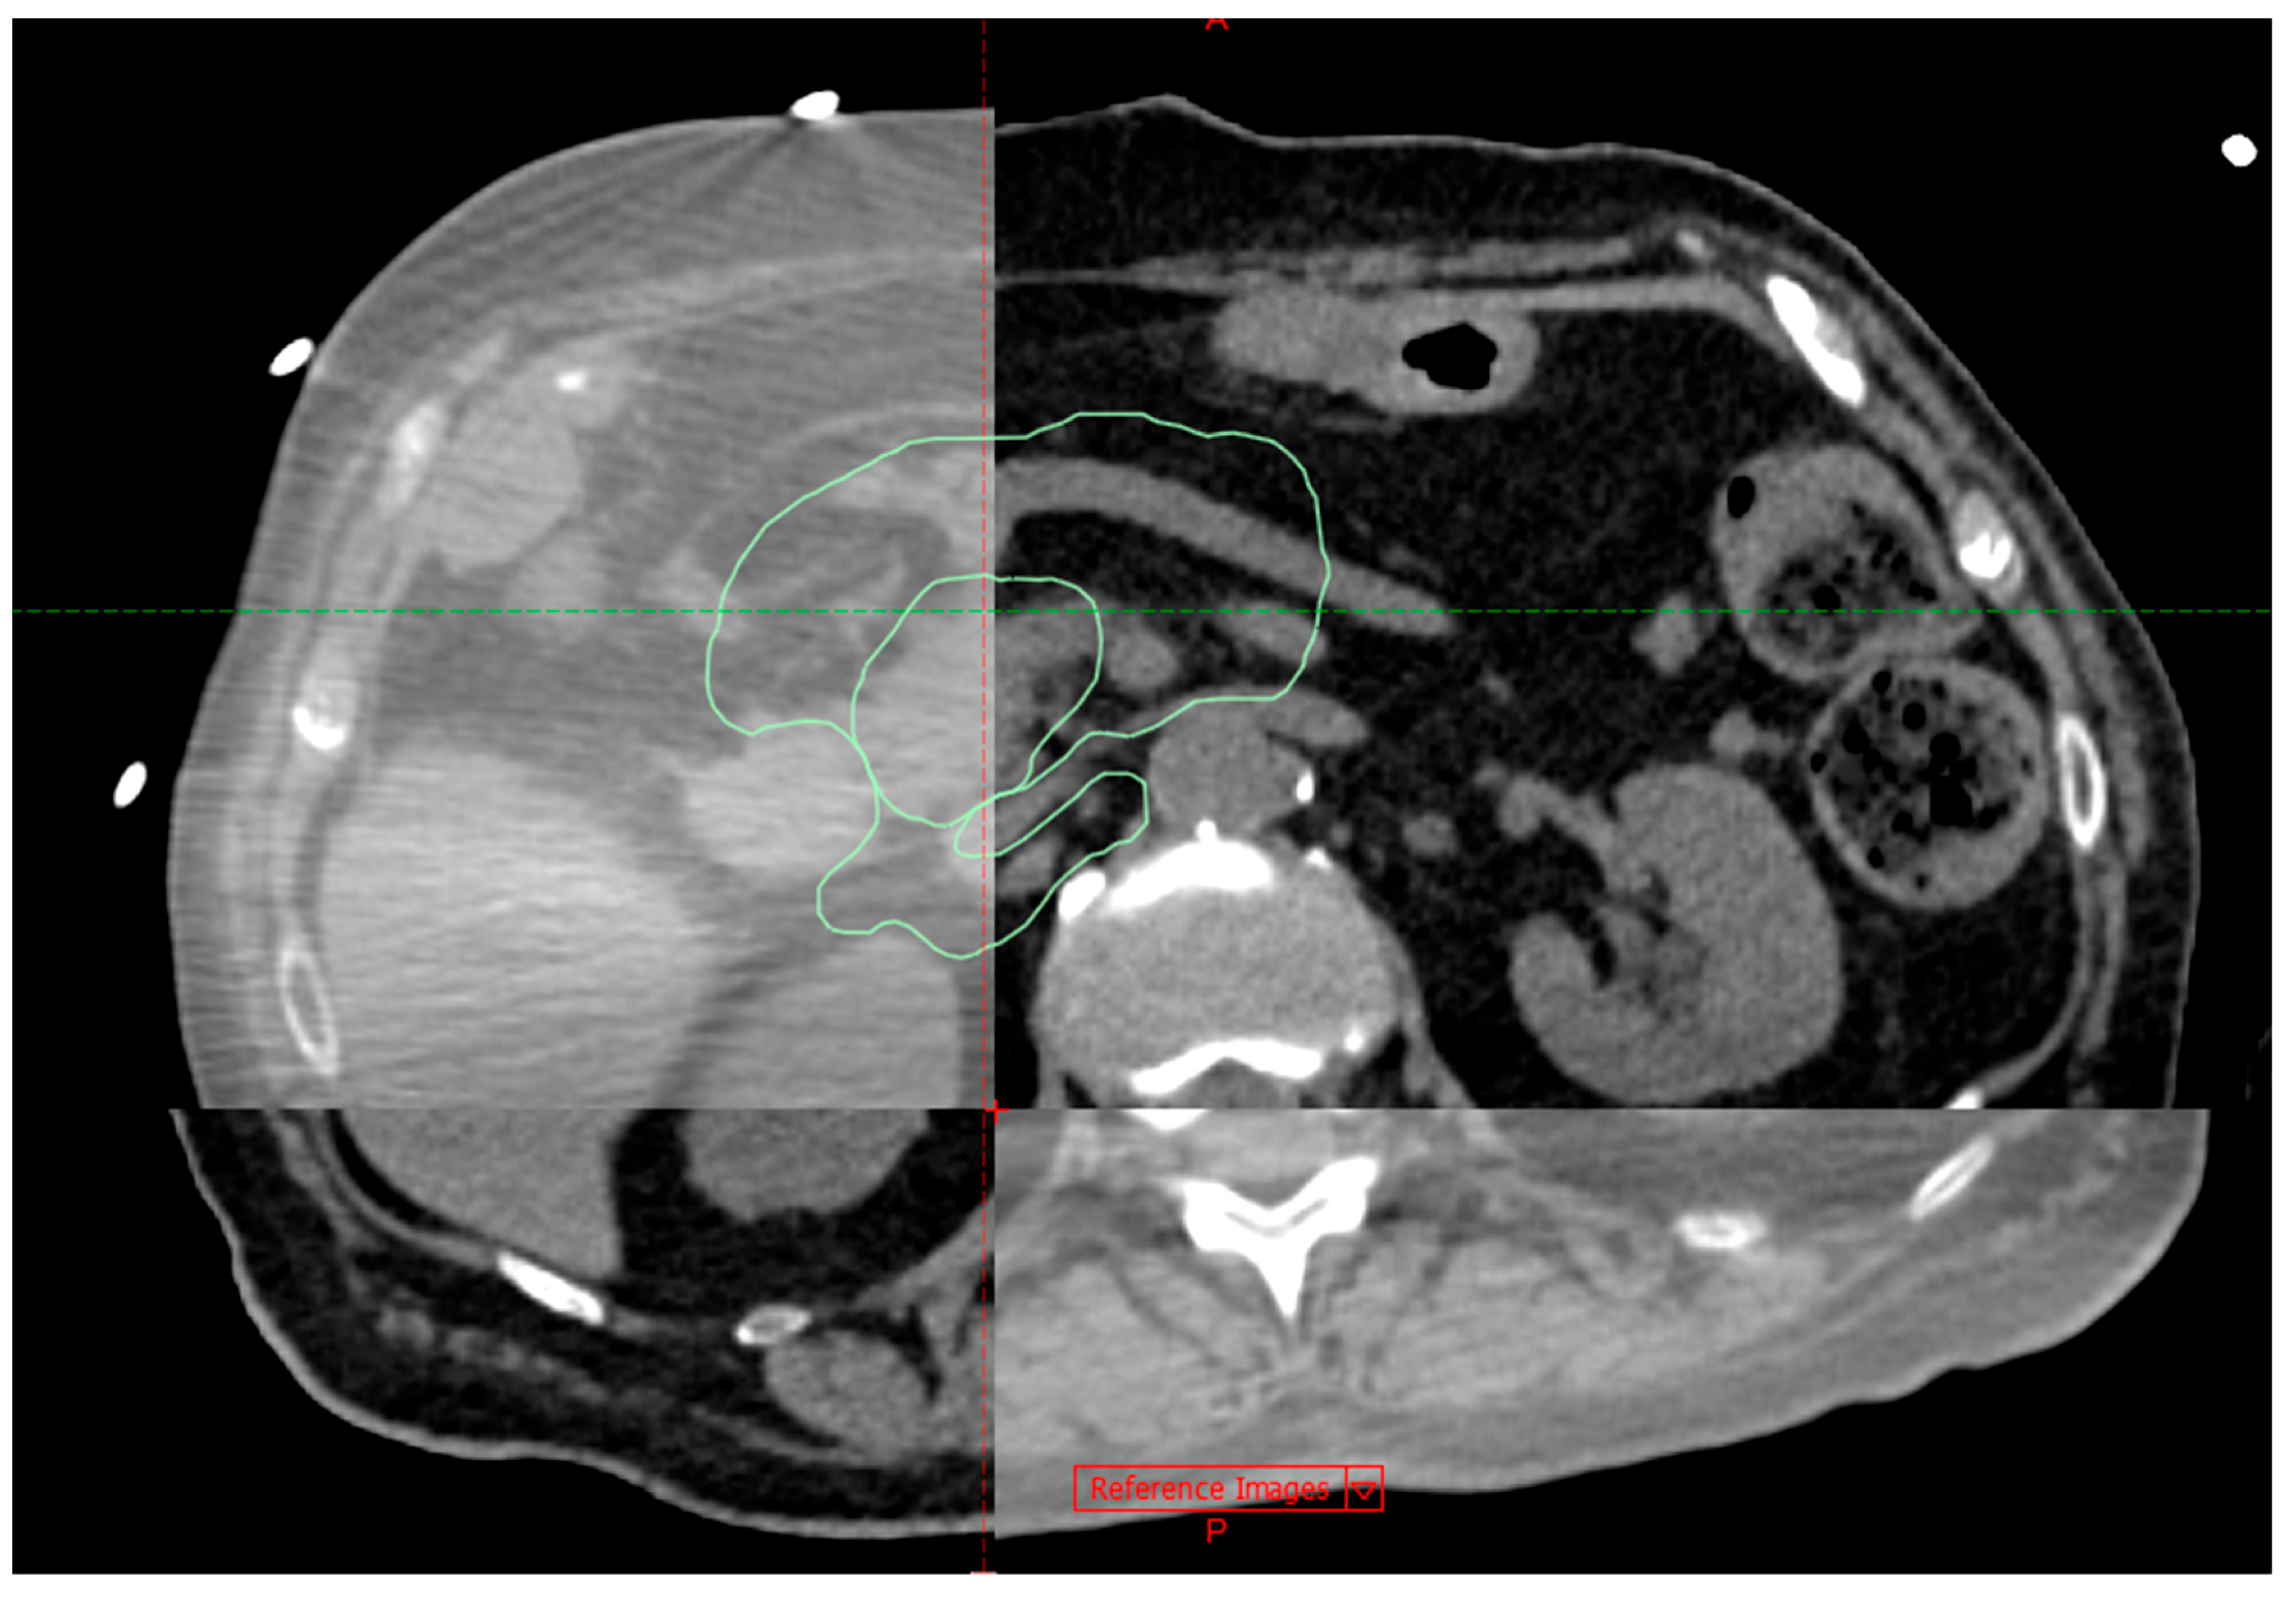
2.4. Optical Surface Guidance
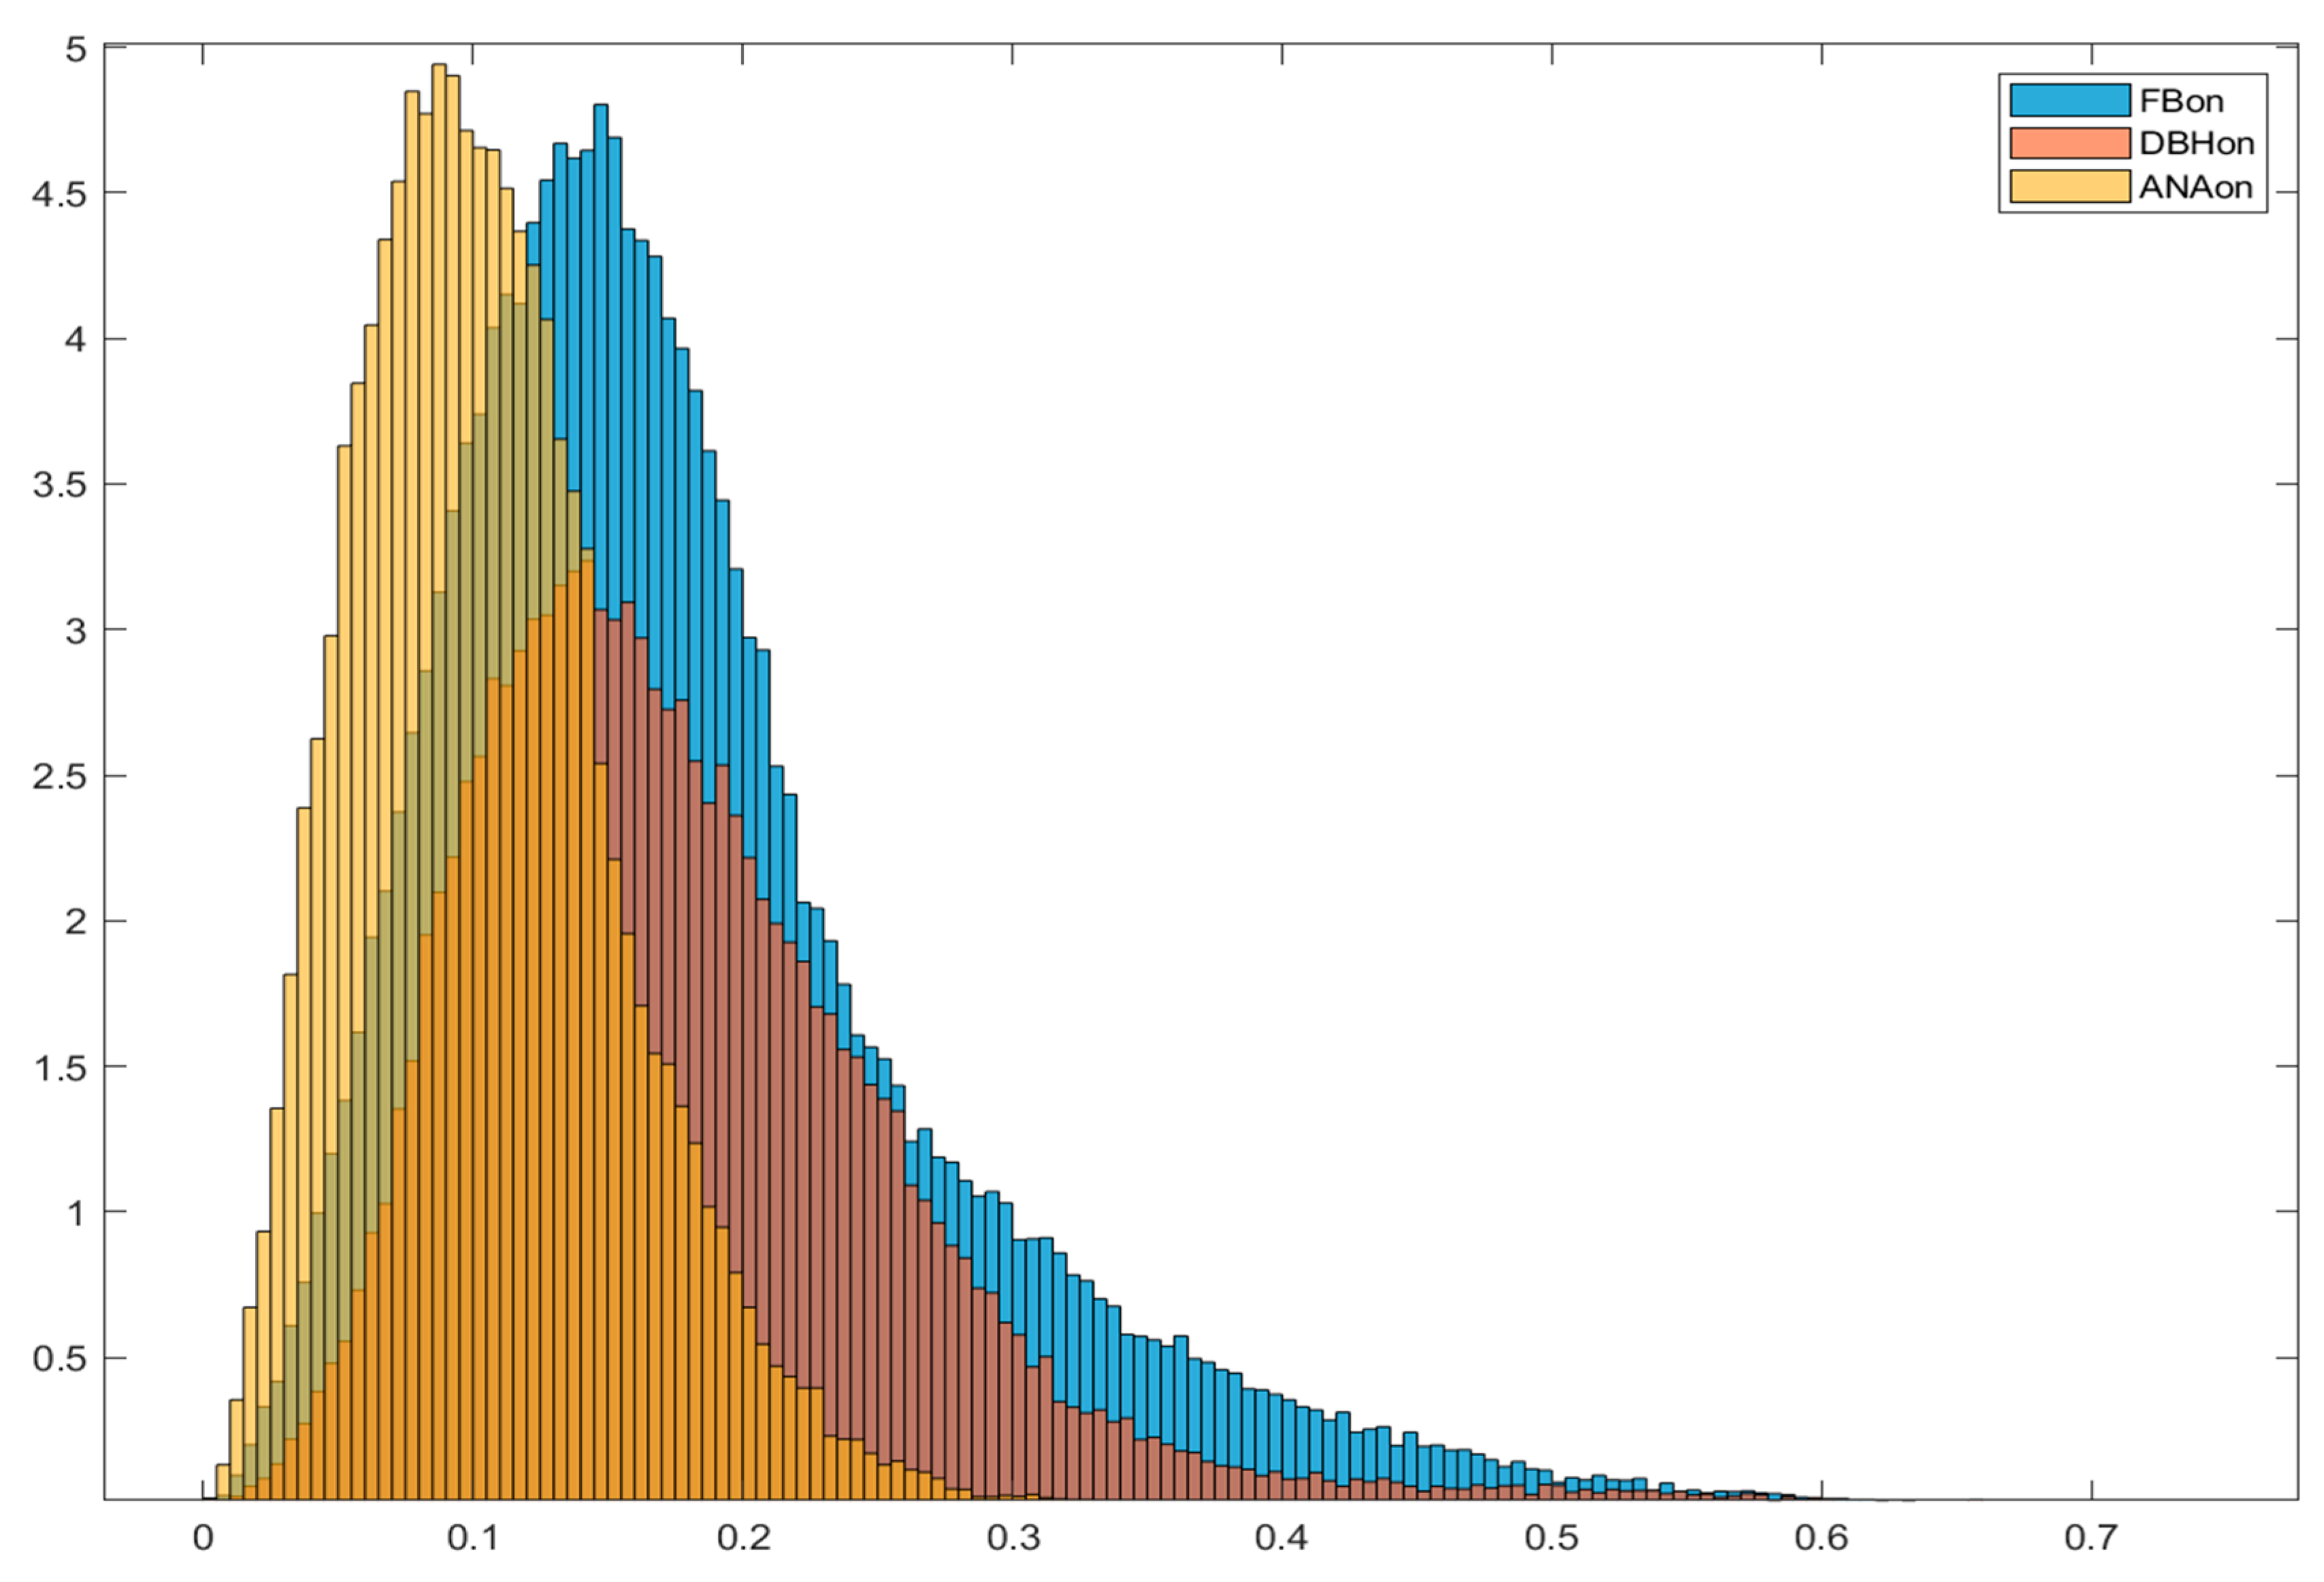
2.5. Tumour Movements During SBRT in TIVA Controlled BH - Assessed by Calypso System
- Movement Analysis and Positioning Accuracy: TIVA controlled BH achieved the smallest geometric displacement (0.05 cm) and rotation (3.8 degrees), indicating improved positioning stability.
- Movement Tracking and Treatment Time: TIVA controlled BH reduces median radial movement during treatment to 0.26 cm with a total treatment time of 46.2 minutes (~2 hours), compared to FB and voluntary BH which have higher movement and longer treatment times. During beam-on, TIVA controlled BH showed the lowest median radial movement (0.1 cm) and longest average treatment interval (19.5 s), indicating better motion control
- Movement Histograms and Data Visualization: Normalized histograms of tracking movement during all treatment phases and beam-on periods confirmed reduced motion with TIVA controlled BH compared to FB and voluntary BH, supporting improved treatment precision.
- Clinical Implications and Future Directions: TIVA controlled BH reduced uncertainties, improved repeatability and imaging, enabling single-fraction treatment with elective lymph nodes irradiation, and eliminating the need for fiducials.
2.6. Stereotactic Ablative Radiotherapy
- The mean dose to the SIB-PTV was considerably higher than the prescription dose,
- No planning constraints on the dose maximums were set, as long as they were inside the SIB-PTV.
- The optimization of the dose distribution was performed with the purpose of achieving a required target coverage of V(98–99.5%) = 80% of the prescribed dose for the SIB-PTV.
- Σ = 0.4 mm, as determined by end-to-end tests; for systemic error
- σ = 2 mm, defined as gating windows; for random error.
- Primary (directly adjacent to pancreas and highly radiosensitive) OARs: (stomach, duodenum, small bowel)
- 2. Other OARs (liver, great vessels, spinal cord, kidneys)
2.7. Response Evaluation and Follow-Up
2.8. Statistical Analysis
3. Results
4. Discussion
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| SBRT | Stereotactic body radiotherapy |
| SABR | Stereotactic ablative radiotherapy |
| LC | Local control |
| BED | Biologically Effective Dose |
| OS | Overall survival |
| FB | Free breathing |
| ITV | Internal Tumour Volume |
| BH | Breath hold |
| CTV | Clinical target volume |
| PTV | Planning target volume |
| MRI | Magnetic resonance imaging |
| LAPC | Locally advanced pancreatic cancer |
| TIVA | Total Intravenous Anaesthesia |
| ACMV | Assist-Control Mechanical Ventilation |
| OSG | Optical surface guidance |
| OAR | Organs at risk |
| ECOG PS | Eastern Cooperative Oncology Group Performance Status |
| MDT | Multidisciplinary team |
| NCCN | National Comprehensive Cancer Network |
| MSCT | Multi-Slice Computed Tomography |
| PET/CT | Positron emission tomography/computed tomography |
| ASA | American Society of Anaesthesiology |
| NIPB | Non-invasive blood pressure |
| IBP | Invasive arterial pressure |
| CBCT | Cone beam CT |
| IG | Image guidance |
| DBC | Default body contour |
| ROI | Region of interest |
| GTV | Gross tumour volume |
| ESTRO | European Society for Radiotherapy and Oncology |
| ASTRO | American Society for Radiation Oncology |
| SIB | Simultaneous integrated boost |
| NCI | National Cancer Institute |
| CTCAE | Common Terminology Criteria for Adverse Events |
| FFLP | Freedom from local progression |
| PFS | Progression-free survival |
| CI | Confidence interval |
| GI | Gastrointestinal |
References
- Tonini, V.; Zanni, M. Pancreatic cancer in 2021: What you need to know to win. World J. Gastroenterol. 2021, 27, 5851–5889. [Google Scholar] [CrossRef] [PubMed]
- Siegel, R.L.; Miller, K.D.; Jemal, A. Cancer statistics, 2020. CA Cancer J. Clin. 2020, 70, 7–30. [Google Scholar] [CrossRef]
- Mizrahi, J.D.; Surana, R.; Valle, J.W.; Shroff, R.T. Pancreatic cancer. Lancet 2020, 395, 2008–2020. [Google Scholar] [CrossRef]
- Moningi, S.; Dholakia, A.S.; Raman, S.P.; Blackford, A.; Cameron, J.L.; Le, D.T.; De Jesus-Acosta, A.M.C.; Hacker-Prietz, A.; Rosati, L.M.; Assadi, R.K.; et al. The Role of Stereotactic Body Radiation Therapy for Pancreatic Cancer: A Single-Institution Experience. Ann. Surg. Oncol. 2015, 22, 2352–2358. [Google Scholar] [CrossRef]
- Reyngold, M.; Parikh, P.; Crane, C.H. Ablative radiation therapy for locally advanced pancreatic cancer: Techniques and results. Radiat. Oncol. 2019, 14, 95. [Google Scholar] [CrossRef]
- NCCN Clinical Practice Guidelines in Oncology: Pancreatic Adenocarcinoma. Version 2.2025. Available online: https://www. nccn.org/professionals/physician_gls/pdf/pancreatic.pdf (accessed on 12 August 2025).
- Dhont J, Harden SV, Chee LYS, Aitken K, Hanna GG, Bertholet J. Image-guided Radiotherapy to Manage Respiratory Motion: Lung and Liver. Clin Oncol (R Coll Radiol). 2020, 32, 792–804. [CrossRef] [PubMed]
- Bussels, B.; Goethals, L.; Feron, M.; Bielen, D.; Dymarkowski, S.; Suetens, P.; Haustermans, K. Respiration-induced movement of the upper abdominal organs: a pitfall for the three-dimensional conformal radiation treatment of pancreatic cancer. Radiother Oncol. 2003, 68, 69–74. [Google Scholar] [CrossRef] [PubMed]
- Brunner, T.B.; Nestle, U.; Grosu, A.-L.; Partridge, M. SBRT in pancreatic cancer: What is the therapeutic window? Radiother. Oncol. 2015, 114, 109–116. [Google Scholar] [CrossRef]
- Huguet, F.; Yorke, E.D.; Davidson, M.; Zhang, Z.; Jackson, A.; Mageras, G.; Wu, A.J.; Goodman, K.A. Modeling Pancreatic Tumor Motion Using 4-Dimensional Computed Tomography and Surrogate Markers. Int. J. Radiat. Oncol. Biol. Phys. 2015, 91, 579–587. [Google Scholar] [CrossRef]
- Lens, E.; van der Horst, A.; Kroon, P.S.; Van Hooft, J.E.; Fajardo, R.D.; Fockens, P.; Van Tienhoven, G.; Bel, A. Differences in respiratory-induced pancreatic tumor motion between 4D treatment planning CT and daily cone beam CT, measured using intratumoral fiducials. Acta Oncol. 2014, 53, 1257–1264. [Google Scholar] [CrossRef]
- Ge, J.; Santanam, L.; Noel, C.; Parikh, P.J. Planning 4-Dimensional Computed Tomography (4DCT) Cannot Adequately Represent Daily Intrafractional Motion of Abdominal Tumors. Int. J. Radiat. Oncol. Biol. Phys. 2013, 85, 999–1005. [Google Scholar] [CrossRef]
- Palta, M.; Godfrey, D.; Goodman, K.A.; Hoffe, S.; Dawson, L.A.; Dessert, D.; Hall, W.A.; Herman, J.M.; Khorana, A.A.; Merchant, N.; et al. Radiation Therapy for Pancreatic Cancer: Executive Summary of an ASTRO Clinical Practice Guideline. Pract. Radiat. Oncol. 2019, 9, 322–332. [Google Scholar] [CrossRef]
- Brunner, T.B.; Haustermans, K.; Huguet, F.; Morganti, A.G.; Mukherjee, S.; Belka, C.; Krempien, R.; Hawkins, M.A.; Valentini, V.; Roeder, F. ESTRO ACROP guidelines for target volume definition in pancreatic cancer. Radiother. Oncol. 2020, 154, 60–69. [Google Scholar] [CrossRef]
- Medical Device Network. Verdict Media Limited. Available online: https://www.medicaldevice-network.com/news/ newsvarian-medical-gets-fda-approval-calypso-soft-tissue-Beacon-transponder-4323298/ (accessed on 14 April 2022).
- Kaučić, H.; Kosmina, D.; Schwarz, D.; Mack, A.; Šobat, H.; Čehobašić, A.; Leipold, V.; Andrašek, I.; Avdičević, A.; Mlinarić, M. Stereotactic Ablative Radiotherapy Using CALYPSO® Extracranial Tracking for Intrafractional Tumor Motion Management-A New Potential Local Treatment for Unresectable Locally Advanced Pancreatic Cancer? Results from a Retrospective Study. Cancers (Basel). 2022, 14, 2688. [Google Scholar] [CrossRef] [PubMed]
- https://www.varian.com/.
- Callery, M.P.; Chang, K.J.; Fishman, E.K.; Talamonti, M.S.; Traverso, L.W.; Linehan, D.C. Pretreatment Assessment of Resectable and Borderline Resectable Pancreatic Cancer: Expert Consensus Statement. Ann. Surg. Oncol. 2009, 16, 1727–1733. [Google Scholar] [CrossRef]
- https://www.intersurgical.com/.
- https://visionrt.com/our-solutions/alignrt/.
- Murphy, J.D.; Christman-Skieller, C.; Kim, J.; Dieterich, S.; Chang, D.T.; Koong, A. A Dosimetric Model of Duodenal Toxicity After Stereotactic Body Radiotherapy for Pancreatic Cancer. Int. J. Radiat. Oncol. Biol. Phys. 2010, 78, 1420–1426. [Google Scholar] [CrossRef] [PubMed]
- Benedict, S.H.; Yenice, K.M.; Followill, D.; Galvin, J.M.; Hinson, W.; Kavanagh, B.; Keall, P.; Lovelock, M.; Meeks, S.; Papiez, L.; et al. Stereotactic body radiation therapy: The report of AAPM Task Group 101. Med Phys. 2010, 37, 4078–4101. [Google Scholar] [CrossRef]
- Eisenhauer, E.A.; Therasse, P.; Bogaerts, J.; Schwartz, L.H.; Sargent, D.; Ford, R.; Dancey, J.; Arbuck, S.; Gwyther, S.; Mooney, M.; et al. New response evaluation criteria in solid tumours: Revised RECIST guideline (version 1. 1). Eur. J. Cancer 2009, 45, 228–247. [Google Scholar] [CrossRef] [PubMed]
- Terlizzi, M.; Limkin, E.; Sellami, N.; Louvel, G.; Blanchard, P. Is single-fraction the future of stereotactic body radiation therapy (SBRT)? A critical appraisal of the current literature. Clin Transl Radiat Oncol. 2023, 39, 100584. [Google Scholar] [CrossRef]
- Sutera, P.A.; Bernard, M.E.; Gill, B.S.; Harper, K.K.; Quan, K.; Bahary, N.; Burton, S.A.; Zeh, H.; Heron, D.E. One- vs. Three-Fraction Pancreatic Stereotactic Body Radiation Therapy for Pancreatic Carcinoma: Single Institution Retrospective Review. Front Oncol. 2017, 7, 272. [Google Scholar] [CrossRef]
- Schellenberg, D.; Goodman, K.A.; Lee, F.; Chang, S.; Kuo, T.; Ford, J.M.; et al. Gemcitabine chemotherapy and single-fraction stereotactic body radiotherapy for locally advanced pancreatic cancer. Int J Radiat Oncol Biol Phys 2008, 72, 678–86. [Google Scholar] [CrossRef]
- Schellenberg, D.; Kim, J.; Christman-Skieller, C.; Chun, C.L.; Columbo, L.A.; Ford, J.M.; et al. Single-fraction stereotactic body radiation therapy and sequential gemcitabine for the treatment of locally advanced pancreatic cancer. Int J Radiat Oncol Biol Phys 2011, 81, 181–8. [Google Scholar] [CrossRef]
- Pollom, E.L.; Alagappan, M.; von Eyben, R.; Kunz, P.L.; Fisher, G.A.; Ford, J.A.; et al. Single- versus multifraction stereotactic body radiation therapy for pancreatic adenocarcinoma: outcomes and toxicity. Int J Radiat Oncol Biol Phys 2014, 90, 918–25. [Google Scholar] [CrossRef]
- Greco, C.; Fuks, Z. Single-Dose Radiotherapy for Prostate Cancer-Lessons Learned From Single-Fraction High-Dose-Rate Brachytherapy-Reply. JAMA Oncol. 2021, 7, 1573. [Google Scholar] [CrossRef]
- Greco, C.; Vazirani, A.A.; Pares, O.; Pimentel, N.; Louro, V.; Morales, J.; Nunes, B.; Vasconcelos, A.L.; Antunes, I.; Kociolek, J.; Fuks, Z. The evolving role of external beam radiotherapy in localized prostate cancer. Semin Oncol. 2019, 46, 246–253. [Google Scholar] [CrossRef] [PubMed]
- Parkes, M.J. Breath-holding and its breakpoint. Exp Physiol. 2006, 91, 1–15. [Google Scholar] [CrossRef] [PubMed]
- Parkes, M.J.; Green, S.; Stevens, A.M.; Clutton-Brock, T.H. Assessing and ensuring patient safety during breath-holding for radiotherapy. Br J Radiol. 2014. [Google Scholar]
- Parkes, M.J.; Green, S.; Stevens, A.M.; Parveen, S.; Stephens, R.; Clutton-Brock, T.H. Safely prolonging single breath-holds to >5min in patients with cancer; feasibility and applications for radiotherapy. Br J Radiol. 2016. [Google Scholar] [CrossRef]
- Parkes, M.J.; Green, S.; Stevens, A.M.; Parveen, S.; Stephens, R.; Clutton-Brock, T.H. Reducing the within-patient variability of breathing for radiotherapy delivery in conscious, unsedated cancer patients using a mechanical ventilator. Br J Radiol. 2016. [Google Scholar] [CrossRef]
- Van Ooteghem, G.; Dasnoy-Sumell, D.; Lambrecht, M.; et al. Mechanically-assisted non-invasive ventilation: a step forward to modulate and to improve the reproducibility of breathing-related motion in radiation therapy. Radiother Oncol. 2019, 133, 132–9. [Google Scholar] [CrossRef]
- West, N.S.; Parkes, M.J.; Snowden, C.; et al. Mitigating respiratory motion in radiation therapy: rapid, shallow, non-invasive mechanical ventilation for internal thoracic targets. Int J Radiat Oncol. 2019, 103, 1004–10. [Google Scholar] [CrossRef]
- Fritz, P.; Kraus, H.-J.; Mühlnickel, W.; Sassmann, V.; Hering, W.; Strauch, K. High-frequency jet ventilation for complete target immobilization and reduction of planning target volume in stereotactic high single-dose irradiation of stage I non-small cell lung cancer and lung metastases. Int J Radiat Oncol Biol Phys. 2010, 78, 136–42. [Google Scholar] [CrossRef]
- Galmén, K.; Freedman, J.; Toporek, G.; Goździk, W.; Harbut, P. Clinical application of high frequency jet ventilation in stereotactic liver ablations – a methodological study. F1000 Res. 2018, 7, 773. [Google Scholar] [CrossRef]
- Audag, N.; Van Ooteghem, G.; Liistro, G.; Salini, A.; Geets, X.; Reychler, G. Intrapulmonary percussive ventilation leading to 20-minutes breath-hold potentially useful for radiation treatments. Radiother Oncol. 2019, 141, 292–5. [Google Scholar] [CrossRef]
- Sala, I.M.; Nair, G.B.; Maurer, B.; Guerrero, T.M. High frequency percussive ventilation for respiratory immobilization in radiotherapy. Tech Innov patient Support Radiat Oncol. 2019, 9, 8–12. [Google Scholar] [CrossRef]
- Emert, F.; Missimer, J.; Eichenberger, P.A.; et al. Enhanced deep-inspiration breath hold superior to high-frequency percussive ventilation for respiratory motion mitigation: a physiology-driven, MRI-guided assessment toward optimized lung cancer treatment with proton therapy. Front Oncol. 2021. [Google Scholar] [CrossRef]
- Van Ooteghem, G.; Dasnoy-Sumell, D.; Lambrecht, M.; et al. Mechanically-assisted non-invasive ventilation: a step forward to modulate and to improve the reproducibility of breathing-related motion in radiation therapy. Radiother Oncol. 2019, 133, 132–9. [Google Scholar] [CrossRef]
- West, N.S.; Parkes, M.J.; Snowden, C.; et al. Mitigating respiratory motion in radiation therapy: rapid, shallow, non-invasive mechanical ventilation for internal thoracic targets. Int J Radiat Oncol. 2019, 103, 1004–10. [Google Scholar] [CrossRef]
- Parkes, M.J.; Green, S.; Stevens, A.M.; Clutton-Brock, T.H. Assessing and ensuring patient safety during breath-holding for radiotherapy. Br J Radiol. 2014. [Google Scholar] [CrossRef]
- Parkes, M.J.; Green, S.; Stevens, A.M.; Parveen, S.; Stephens, R.; Clutton-Brock, T.H. Safely prolonging single breath-holds to > 5 min in patients with cancer; feasibility and applications for radiotherapy. Br J Radiol. 2016. https:// doi.org/ 10. 1259/ bjr. 20160 194., Parkes MJ, Green S, Kilby W, Cashmore J, Ghafoor Q, Clutton-Brock TH. The feasibility, safety and optimization of multiple prolonged breath-holds for radiotherapy. Radiother Oncol. 2019.

| Primary OAR (Stomach, Duodenum, Small Bowel) |
Dmax (0.03 cm3) < 23 Gy V(20 Gy) < 3.3 cm3 V(15 Gy) < 9.1 cm3 |
|---|---|
| Liver | V(9.1 Gy) < 700 cm3 |
| Great Vessels | Dmax < 37 Gy |
| Spinal Cord | Dmax < 14 Gy |
| Kidneys | V(8.4 Gy) < 200 cm3 |
| End Points | Median/Mean | 1 Year |
| FFLP | 23 months * | 100% |
| PFS | 12 months (95% CI: 9.5 to 14.4) | 85.5% |
| OS | 26.7 months ** (95% CI: 23,5 to 29,9) | 90.9% |
| Acute (patients, %) | Late (patients, %) | |
|---|---|---|
| Grade 1 | 35 (63.6%) | 4 (7.3%) |
| Grade 2 | 9 (16.4%) | none |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).