

Submitted:
07 August 2026
Posted:
07 August 2026
You are already at the latest version
Abstract
The glymphatic system is a brain-wide perivascular network that facilitates cerebrospinal fluid-interstitial fluid exchange and the clearance of metabolic waste. Growing experimental and clinical evidence suggests that glymphatic dysfunction may represent a convergent upstream mechanism linking aging, neuroinflammation, and neurodegeneration. In this narrative review, we synthesize human imaging, clinical, and translational evidence implicating glymphatic dysfunction across major neurodegenerative diseases and integrate these findings with emerging data supporting its role in chronic low-grade inflammation associated with aging (inflammaging). We further discuss how alterations in the gut microenvironment may remotely influence glymphatic function and contribute to neurodegeneration through the gut–brain axis. Although supported by extensive preclinical evidence, studies in humans increasingly demonstrate impaired glymphatic function in several neurodegenerative disorders, most assessed using diffusion tensor imaging along the perivascular space (DTI-ALPS) index. Glymphatic dysfunction is associated with cognitive decline, motor impairment, and disease progression. Aging-related alterations in astrocytic function, aquaporin-4 polarization, blood-brain barrier integrity, and perivascular fluid dynamics provide mechanistic links between inflammaging and glymphatic failure. Gut dysbiosis may further exacerbate these processes by promoting central nervous system inflammation and vascular dysfunction. Together, these findings identify the glymphatic system as a clinically relevant pathway in neurodegeneration that may be regulated by aging-associated neuroinflammatory mechanisms involving the gut-brain axis. Finally, we discuss lifestyle factors that influence glymphatic function and propose a unified framework positioning glymphatic dysfunction as a central integrator of impaired brain clearance, with potential implications for biomarker development, clinical assessment, and disease-modifying therapeutic strategies in neurodegenerative disorders.
Keywords:
glymphatic system
; neurodegenerative diseases
; neuroinflammation
; inflammaging
; gut-brain axis
; aquaporin-4
; DTI-ALPS
1. Introduction
Efficient clearance of metabolic waste and interstitial solutes is essential for maintaining central nervous system (CNS) homeostasis. Although brain lacks a conventional lymphatic vasculature within its parenchyma, the last decade scientific findings suggest the existence of a complicated mechanism, coined as the glymphatic system, which is responsible for the removal of macromolecules, neurotoxic proteins, and excess fluid [1,2]. Since the description of the glymphatic system, our understanding of brain fluid dynamics has been fundamentally reshaped and a mechanistic framework with direct relevance to aging and neurodegeneration is increasingly unveiled.
The glymphatic system is suggested to be a brain-wide perivascular network that facilitates the exchange between cerebrospinal fluid (CSF) and interstitial fluid (ISF), thereby enabling convective transport of solutes through the brain parenchyma [3]. According to the prevailing theory, CSF enters the brain along periarterial spaces, driven by arterial pulsatility and pressure gradients, mixing with ISF within the interstitium [4]. The astrocytic endfeet ensheathing the cerebral vasculature is considered a key structural element of glymphatic efficiency, by forming the outer boundary of perivascular spaces, expressing aquaporin-4 (AQP4) water channels that enable glymphatic flow. Proper polarization of AQP4 channels at the perivascular astrocytic endfeet is of crucial importance for the efficient waste clearance [5]. After traversing the interstitial compartment, fluid and solutes exit the brain along perivenous spaces, ultimately draining toward meningeal lymphatic vessels and cervical lymph nodes [3]. The glymphatic system via this pathway is suggested to contribute to the clearance of neurotoxic proteins, including amyloid-β (Aβ) [1], tau [6] and α-synuclein (SNCA) [7] (Figure 1).
Aging has been proposed to exert a profound impact on glymphatic structure as seen with loss of perivascular AQP4 polarization [8], vascular stiffness [9] and altered CSF dynamics [10]. Glymphatic function is also altered with advancing age [11] possibly due to reductions in arterial pulsatility [12] and astrocytic reactivity [13]. Chronic low-grade immune activation, also known as inflammaging, further contributes to these changes.
Gut dysbiosis leads to increased expression of pro-inflammatory cytokines resulting in systemic inflammation. Inflammatory mediators from the gut may enter the CNS and impair glymphatic function [14]. Moreover, the production of neurotransmitters and microbial metabolites from the gut may interfere with the circadian rhythms thus leading to sleep disturbances [15]. Given the positive impact of sleep on glymphatic activity [4], any sleep disturbance or disorder may lead to the accumulation of neurotoxic waste in the brain, potentially contributing in excessive neuroinflammation that is present in major CNS disorders.
Given its proposed role in clearing aggregation-prone proteins and inflammatory mediators, there is increasing evidence highlighting the potential implication of glymphatic system in neurodegeneration as a convergent mechanism in multiple CNS disorders [16,17,18,19,20,21,22,23]. Although direct monitoring of glymphatic flow in humans remains challenging, several in vivo imaging approaches have been developed to infer glymphatic function [24]. Contrast-enhanced and contrast-free magnetic resonance imaging (MRI) are among the in vivo techniques that can be applied to humans. The former is invasive and requires the injection of a paramagnetic contrast agent, while the latter analyzes CSF movements without the need for a tracer. Consequently, contrast-free MRI techniques have become the primary tools in human studies, with diffusion tensor imaging along the perivascular space (DTI-ALPS) being the most widely used technique. DTI-ALPS quantifies directional water diffusivity along perivascular spaces, particularly in the white matter, providing an indirect index of perivascular fluid transport. Although there are several limitations in the reflection of glymphatic function from the estimation of the DTI-ALPS index, it is widely employed in a plethora of studies tackling neurodegenerative disorders [25]. Additional MRI-based markers monitor enlarged perivascular space (ePVS) burden [26] and choroid plexus volume [27] that are used separately or in combination with the DTI-ALPS index.
The scope of this review is to synthesize existing preclinical and translational evidence for glymphatic system dysfunction in neurodegenerative diseases. The last part is dedicated to the discussion of the physiological regulators of glymphatic activity. We build upon this synthesis while we integrate emerging concepts of inflammaging and gut-brain axis interactions. Our goal is to highlight the possibility of a systemic nature of the glymphatic system that may contribute to CNS disorders onset. We additionally aim to underscore the importance of the clinical assessment of waste clearance mechanisms towards the unraveling of useful insights for future diagnostic and therapeutic strategies.
2. Neurodegenerative Diseases
2.1. Alzheimer's Disease (AD)
Expression of AQP4 has been reported to correlate with advancing age while loss of its perivascular localization is associated with increased amyloid burden and higher Braak stage [28]. In an experimental model of AD (5XFAD mice) where AQP4 was coupled with a-syntrophin (Snta1), deletion of the latter allowed for controlled depolarization of AQP4 without alterations in its expression [29]. Both deficiency and mislocalization of AQP4 resulted in increased parenchymal Aβ plaque formation and depositions in Snta mice compared to their littermates. Furthermore, human post-mortem case series analysis demonstrated that the loss of perivascular localization of AQP4 in cortical gray matter was more evident in patients with AD compared to subjects with earlier stages of cognitive decline [30]. Genetic analysis has further unveiled AQP4 polymorphisms that are associated with higher risk of cognitive decline [31] and modification in Aβ uptake [32]. However, others have reported a protective role of AQP4 deficiency leading to mitigated astrogliosis [33], neuronal apoptosis and uptake of Aβ [34].
Glymphatic flow has been reported to be dysregulated following depletion or pharmacological inhibition of AQP4 in the Aβ precursor protein/presenilin 1 model (APP/PS1) [33], the 5X FAD model [35] and tauopathy models [6,18,36]. In all instances glymphatic system dysregulation was associated with toxic accumulation of Aβ and tau, astroglial atrophy, loss of synaptic proteins [33], memory deficits, behavioral impairment and neuronal dysfunction [35]. Suppression of clearance of toxic waste following deletion of AQP4 is further supported by the slowing down of CSF influx by almost 70% [1]. Particularly for models of tauopathy, impairment of glymphatic flow seems to take place in specific brain regions, such as the rostral cortex, which are affected early during tau deposition [18]. Glymphatic flow stagnation in these areas is associated with increased volume changes that are potentially implicated in neurodegeneration and diminished cognitive performance [6,36].
Experimental results of AQP4 deficiency widely coincide with findings from studies assessing the effects of meningeal lymphatics disruption that are involved in the drainage of CSF and ISF to cervical lymph nodes. Surgically disrupted meningeal lymphatics in AD mouse models increased Aβ deposition both in the meninges and the brain tissue, accompanied with increased inflammation and behavioral impairment [37]. Disrupted meningeal lymphatics were further correlated with a pro-inflammatory microglial molecular signature like what is observed in AD pathogenesis [38]. Given that the dominating microglial phenotype is suggested to be the key mediator for the association between tauopathy and glymphatic dysfunction on the one hand [39,40], and that Aβ accumulation in the CSF may halt the glymphatic influx on the other hand [41], a waste clearance mechanism dysfunction driven by pathological features observed in AD pathogenesis is further reinforced.
Advanced imaging studies have revealed consistent clinical symptoms associated with glymphatic dysfunction across the AD spectrum. These studies aimed to link glymphatic dysfunction to core AD pathology comparing DTI-ALPS values in patients with AD and patients with prodromal stages of AD pathogenesis, such as patients with mild cognitive impairment (MCI) and subjective cognitive decline (SCD), as well as healthy individuals [16,20,42,43,44,45]. Glymphatic dysfunction was reported in symptomatic AD compared to healthy individuals [42]. Abnormal DTI-ALPS is already present in patients with SCD suggesting that glymphatic dysfunction may be a prodromal symptom at a very early preclinical-risk stage [20] supported by PVS enlargement even before perivenous efflux impairment [19]. Lower DTI-ALPS values were strongly associated with greater amyloid burden [19,20,42,43] and reduced cognitive function [19,20,42]. Interestingly, Aβ and tau burden partially or fully mediate the association of low DTI-ALPS index to progression from prodromal stages to an AD phenotype [16,43] and deterioration of cognitive performance [20,43]. Lower DTI-ALPS index is further associated with enlarged PVS [45], while free water in white matter was correlated with reduced scores in cognitive and functional scales [19]. No significant risk associations were observed when patients with MCI were stratified by sex, age or APOE ε4 status [16].
These findings suggest a clinically meaningful association between reduced water diffusivity and neuronal loss potentially linking glymphatic dysfunction to AD pathology. Glymphatic dysfunction in AD is further supported by a two-stage proteomic analysis in patients with AD and MCI that shows that proteins associated with the proper function of glymphatic system are mainly involved in neurodegenerative processes, immunity and inflammation [46].
2.2. Parkinson's Disease (PD)
Deficiency of AQP4 in established PD experimental models has been shown to drive hypersensitive responses in mice following stimulation with neurotoxic agents [47,48]. These reactions were suggested to be due to increased astrogliosis, since an increased number of astrocytes was observed following AQP4 deficiency in basal as well as neurotoxic conditions [49]. Genetic evidence from PD patients further supports the role of AQP4 in the disease pathogenesis, with patients carrying the AQP4 rs68006382 being associated with faster transition to lower cognitive performance [50].
Reduced clearance of SNCA has been observed following deletion or pharmacological inhibition of AQP4 in experimental models overexpressing the human A53T-SNCA [7]. Accumulated SNCA was associated with neuronal loss and exacerbated symptoms. Additionally, in PD models where SNCA preformed fibrils (PFFs) were injected intrastriatally, glymphatic flow stagnation was associated with behavioral impairments [51]. Furthermore, blockage of meningeal lymphatic drainage, via cervical lymph nodes ligation, resulted in impaired clearance of SNCA and depolarization of AQP4, further highlighting the impact of the clearance mechanisms in PD pathogenesis [52].
A direct feedback loop between glymphatic function impairment and SNCA aggregation has been proposed. Overexpression of A53T-SNCA in mice has been shown to suppress glymphatic flow via modulation of the expression and depolarization of AQP4 [7]. Subsequent blockage of PVS by SNCA aggregates may not further permit the glymphatic efflux. Alternatively, targeted expression of mutated human SNCA in astrocytes drives the loss of AQP4 perivascular localization associated with enhanced astrogliosis in the brainstem and spinal cord of symptomatic mice potentially linking neuroinflammation and glymphatic system dysfunction [53].
Glymphatic function has been consistently reported to be deregulated in PD patients, commonly reflected by a lower DTI-ALPS index compared to matched healthy individuals across cross-sectional and longitudinal cohorts [23,54,55,56,57]. Lower DTI-ALPS index is associated with greater motor severity, as measured by higher Unified Parkinson's Disease Rating Scale (UPDRS)-III scores [55,57,58], whereas baseline glymphatic dysfunction may predict motor dysfunction progression, with lower DTI-ALPS associated with faster worsening of UPDRS-III scores [23] and increased risk of clinical milestones, such as wheelchair dependence [59]. Furthermore, lower DTI-ALPS is associated with worse global cognition, as measured by lower scores in the Mini-Mental State Examination (MMSE) and Montreal Cognitive Assessment (MoCA) scales in several PD cohorts [57,58], while baseline DTI-ALPS values can predict longitudinal cognitive decline [57]. However, findings from other PD cohorts have not been able to replicate this association [23].
Lower DTI-ALPS values, further, seem to decline with advancing age, with older PD subgroups demonstrating stronger negative correlations [23]. Increased age at disease onset is also associated with decreased DTI-ALPS values, suggesting that aging-related glymphatic dysfunction may be associated with the disease onset [56]. Moreover, impaired glymphatic function has been linked with sleep disturbances [58,60] possibly associated with prodromal PD phenotypes although this association is emerging more clearly in clinically meaningful PD subgroups [58]. Female patients have shown higher DTI-ALPS values compared to males at baseline and after of one-year of follow-up [23]; however, other studies do not confirm sex-specific differences [58].
A potential direct link between the glymphatic system impairment and the subsequent neurodegeneration in PD patients may be speculated based on indications about a positive association of the DTI-ALPS index with regional cortical volumes [54]. Mediation analysis demonstrated that cortical degeneration partially mediates the association between glymphatic dysfunction and cognitive impairment. Given that accumulation of SNCA is most often detected in the regional cortex, this evidence suggests a bidirectional mechanism through which SNCA aggregates may disturb the AQP4 anchoring in the astrocytic endfeet, resulting in glymphatic clearance abolition, further promoting its own aggregation.
2.3. Non-AD Dementia
Categories of non-AD dementia encompass a variety of conditions that cause cognitive decline, distinct from AD. Among several conditions, such as frontotemporal dementia (FTD) and idiopathic normal pressure hydrocephalus (iNPH), the occurrence of glymphatic system dysfunction is suggested. The FTD group characterizes brain disorders that primarily affect the frontal and temporal lobes with the most common clinical syndrome being the behavioral variant FTD (bvFTD) which is associated with atrophy of the frontal and anterior temporal lobes [61]. The pathology of FTD is characterized by intracytoplasmic inclusions of aggregated neuronal and glial proteins, such as tau and TDP-43, that eventually lead to disruption of neuronal homeostasis and subsequent cell death [62,63]. On the other hand, iNPH pathogenesis is associated with altered CSF dynamics, enlarged brain ventricles and vascular abnormalities [64].
Experimental findings from studies employing vascular/mixed-dementia experimental models including the microscopic microinfarcts model [65], the hyperhomocysteinemia model of vascular cognitive impairment [66] and a mixed dementia rat model, namely SHRSP/FAD rats [67] point towards a systemic glymphatic dysfunction. The polarization of AQP4 was found to be disturbed in all experimental models while associations with cognitive decline [66], reactive gliosis [68], dilated PVS and delayed waste clearance [65] were observed. These initial findings suggest that glymphatic system dysregulation may emerge as a unifying contributor across diverse dementia types.
Significantly higher levels of AQP4 have been reported in FTD patients compared to subjects not affected by neurodegenerative diseases. A significant, positive correlation was further detected between AQP4 and total tau levels pointing towards enhanced astrogliosis [69]. On the contrary, decreased expression [70] and reduced density of AQP4 in astrocytic endfoot membranes has been reported in biopsies of iNPH patients compared to reference individuals [71].
Glymphatic dysfunction has been shown in patients with FTD syndromes and genetic FTD [22,72,73]. Particularly for bvFTD, increased waste accumulation suggestive of glymphatic abnormality has been reported in characteristic areas of FTD pathology, such as the forebrain and midbrain areas [72]. Across FTD variants, DTI-ALPS abnormalities are subtype-specific and are related to whole-brain white matter hyperintensities, cognitive performance and cortical thickness, suggesting that worse glymphatic function is linked to specific patterns of cortical neurodegeneration [73]. Furthermore, assessment of glymphatic function across symptomatic/presymptomatic mutation carriers and non-carriers, demonstrated that the DTI-ALPS index was lower in symptomatic compared to presymptomatic patients and non-carriers [22]. The index was further associated with disease severity and faster worsening suggesting that glymphatic dysfunction may predispose the disease course based on the different genetic background and disease stage [22].
Similar findings have been reported for cohorts of patients with iNPH. Clearance of gadobutrol has been reported to be delayed in iNPH patients compared to healthy individuals showing increased persistence in the brain parenchyma [74,75,76]. Compared with non-cognitively affected patients, iNPH patients show higher medial temporal lobe atrophy scores and ventricular enlargement (Evans’ index) and reduced entorhinal cortex thickness, tying impaired glymphatic clearance with structural vulnerability in memory-related regions [76]. These observations suggest that reduced clearance of toxic metabolites may underly pathology in non-AD dementia.
2.4. Multiple Sclerosis (MS)
Increased expression and loss of perivascular localization of AQP4 has been shown in the brain and spinal cord tissues in the most commonly used experimental model of MS, experimental autoimmune encephalomyelitis (EAE) [77,78,79]. Deficiency of AQP4 in myelin oligodendrocyte glycoprotein (MOG)-induced EAE, as well as in adoptive transfer models, was associated with mitigated neuroinflammation and diminished clinical symptoms compared to wild-type littermates [80]. Moreover, following adenovirus-mediated overexpression of AQP4 in astrocytes, the latter acquired an enhanced pro-inflammatory profile, further reinforcing the role of AQP4 in mediating the MS inflammatory cascade [80].
Widespread parenchymal localization of AQP4 is associated with impairment of parenchymal CSF circulation in the spinal cord of EAE-induced mice [79]. Although deceleration of glymphatic flow could be plausibly based on the heavy inflammatory burden of MS or by the hypersecretion of CSF [81], an increasing body of research points towards glymphatic system dysfunction in patients with MS. Reduced DTI-ALPS values have been consistently reported to be reduced in cohorts of MS patients compared to age- and sex-matched healthy individuals [17,82]. Although glymphatic deregulation is apparent both in the relapsing remitting and the progressive phenotype of MS, an enhanced decline is observed for the latter, suggestive of a parallel trajectory along clinical course [83]. Lower DTI-ALPS index is further associated with worse clinical disability, as estimated with the Expanded Disability Status Scale, and longer disease duration [17,83].
Impaired glymphatic function seems to co-occur with structural brain damage and global brain volume changes. Lower DTI-ALPS index was reported to be associated with higher white matter and cortical lesion volume, deep grey matter atrophy and reduced fractional anisotropy [17]. Additionally, larger choroid plexus volume correlates with lower DTI-ALPS index in patients with MS, while both indices were associated with higher total, periventricular, and juxtacortical white matter lesion volumes and lower brain, thalamic and cortical volumes [82]. Interestingly, the DTI-ALPS index was reported to partially mediate the association between increased choroid plexus volume and structural brain changes, suggesting that glymphatic impairment links altered CSF dynamics to tissue damage [82].
Choroid plexus enlargement may represent a key factor in glymphatic system dysfunction in MS, potentially driven by increased infiltration of inflammatory cells and soluble mediators [84,85]. Given that choroid plexus is suggested to produce the vast majority of CSF, any structural distortion may potentially lead to stagnation of CSF flow [27]. Given that choroid plexus enlargement takes place during the early stages of MS, correlations with increased presence of immune cells [86], clinical disability and cognitive dysfunction [87] point towards a more progressive phenotype [27].
Collectively, MS-specific aberrations in choroid plexus volume may confer to persistent inflammation that may lead to the impediment of glymphatic flow and subsequent impairment of the clearance of immune toxic mediators [82]. Impaired glymphatic function is associated with both demyelinating and neurodegenerative events, therefore the exact impact of glymphatic system deregulation in the MS pathogenesis warrants further investigation.
2.5. Autoimmune Encephalitis
Autoimmune encephalitis is an umbrella term for multiple disorders that are characterized by the immune system activation against CNS epitopes such as N-methyl-D-aspartate receptor [88]. Concrete findings regarding the expression of AQP4 in autoimmune encephalitis are lacking, although recently the rare coexistence of autoantibodies against neuronal or glial epitopes representative of autoimmune encephalitis and against AQP4 has been reported [89]. This clearly distinguishes the disease mechanisms of autoimmune encephalitis from neuromyelitis optica spectrum disorder.
Only one study has recently evaluated the glymphatic function in patients with autoimmune encephalitis [90]. Patients with autoimmune encephalitis had lower DTI-ALPS values compared to age- and sex-matched healthy individuals. Low baseline DTI-ALPS index was associated with a decline in cognitive function, as estimated with MMSE and MOCA scales, while an increased risk of long-term cognitive impairment was linked to lower DTI-ALPS index. These observations were confirmed across different subgroups depending on the target of the autoimmune pathogenesis, while the increased expression of pro-inflammatory cytokines partially mediate the association of glymphatic function deterioration with cognitive decline [90]. Although preliminary, these observations suggest a link between glymphatic system impairment and cognitive decline with inefficient clearance of pro-inflammatory cytokines.
2.6. Stroke
The presence of abundant toxic extracellular fluids in areas of liquefactive necrosis leads to atrophy, cytotoxic edema, and neuronal loss in regions adjacent to the infarct for weeks following stroke [91]. Therefore, potential dysregulation of waste clearance mechanisms during stroke may contribute to the impartial recovery. The glymphatic flow could be plausibly hampered from the rapid inflow of blood and CSF in the PVS resulting in brain edema and tissue swelling [92,93,94]. Evidence points to the increased enlarged PVS burden, particularly in the basal ganglia and hippocampus, as a significant risk factor of incident stroke and intracerebral hemorrhage (ICH) [95,96]. Additionally, patients with spontaneous ICH and increased size of PVS in centrum semiovale demonstrate increased vascular amyloid burden [97] while in patients with subarachnoid hemorrhage (SAH) a reduced serum/CSF ratio of neurofilament light polypeptide has been observed [98]. These findings point towards impaired glymphatic efflux and reduced leakage to the draining lymph nodes.
The expression of AQP4 in SAH, ICH and ischemic stroke experimental models has been reported to increase very early during induction [99], suggesting its crucial role in mediating glymphatic function integrity. However, it is difficult to define the role of AQP4 in stroke and related conditions due to the contradictory results reported following its deficiency in experimental models. Knockout of AQP4 has been shown to cause enhanced neuronal loss and BBB disorganization following SAH induction [93,100], brain edema [101], as well as pronounced microglial activation in the middle cerebral artery occlusion (MCAO) model compared to wild-type mice [102]. On the other hand, cerebral edema is reported to decrease in AQP4 knockout mice early post MCAO induction [103,104] while reduced infarct volumes following APQ4 inhibition have been also reported [105]. Therefore, defining the role of AQP4 and subsequently the regulation of glymphatic flow in stroke warrants further research.
However, experimental evidence suggests that glymphatic dysfunction occurs during stroke and related conditions. Rodent models of SAH, whether induced by endovascular perforation or blood injection into the cisterna magna, are characterized by a significant and prolonged disruption of CSF circulation and glymphatic function [93,106,107,108] as well as reduced drainage to deep cervical lymph nodes associated with AQP4 depolarization [106]. Findings from a non-human primate model of SAH further corroborates the dysregulation found in rodent models [109]. Glymphatic system dysfunction during the acute phase of multiple experimental models seems to predominantly occur in the substantia nigra and the ventral thalamic nucleus (VTN) areas [110]. Deregulation of glymphatic flow has been associated with accumulation of tau protein and immune cells, glial cell activation, neuroinflammation, neuronal apoptosis [106] and cognitive dysfunction [111] representing extended neuropathological damage.
Accumulating neuroimaging evidence indicates that glymphatic function is consistently impaired in stroke patients, most inferred from reductions in the DTI-ALPS index. Across ischemic and hemorrhagic stroke subtypes, patients demonstrate lower DTI-ALPS values compared to healthy individuals [112,113,114,115,116,117] and disease-specific subgroups [21], supporting the presence of glymphatic dysfunction post-stroke.
In patients with subacute ischemic stroke, significantly lower DTI-ALPS values compared to healthy subjects indicate reduced perivascular fluid transport after ischemic injury [114]. During the chronic phase (3–12 months), stroke survivors demonstrated persistent reduced DTI-ALPS values versus healthy subjects at both 3 months and 1 year, suggesting prolonged glymphatic disturbance beyond the acute/subacute period [116]. This observation supports the existence of long-lasting glymphatic dysfunction, particularly in the hemisphere ipsilateral to infarction [113,114,116,118]. Similar, glymphatic function impairment has been demonstrated in the lesion compared to contralateral side in patients with spontaneous ICH [112]. Patients with cerebral infraction classified in a good prognosis group based on modified Rankin Scale had increased DTI-ALPS values compared to those classified in the poor prognosis group [21]. Preserved glymphatic function was associated with better neurological outcomes and better psychological recovery pointing towards a prognostic value of DTI-ALPS [21]. Particularly for patients with cerebral small vessel disease (CSVD), a condition that causes approximately 20% of strokes [119], reduction in DTI-ALPS indices correlated with enlarged PVS in basal ganglia and existence of lacunes [120], cerebral venous integrity [121] and vascular risk factors [117].
Findings from these studies suggest an association between glymphatic dysfunction and motor and cognitive functions. In subacute ischemic stroke, the DTI-ALPS index correlated positively with Fugl-Meyer motor scores, supporting a relationship between greater glymphatic impairment and worse motor function [114]. Furthermore, the DTI-ALPS index was correlated with 6-month post-stroke cognitive impairment [113]. In concordance with this, the DTI-ALPS index has been reported to be useful for prediction of future dementia risk in patients with lacunar strokes and confluent white matter hyperintensities [122]. Weak correlations also emerged at 3 months between the DTI-ALPS index in the lesioned hemisphere and motor and memory scales, although this correlation could not be detected at 1 year of follow-up, suggesting that the correlation may be transient [116].
The time since stroke onset and stroke duration are among the factors that suggest a time-dependent relationship between glymphatic activity and disease course. Values of DTI-ALPS increase along time since disease onset [113,116,118] while in the sICH cohort, the lesion-side DTI-ALPS index was correlated with disease duration [112]. These observations may represent the activation of organism towards partial recovery after early impairment due to potential remodeling or reversibility of glymphatic function during rehabilitation [113,118]. Application of standard reperfusion therapy results also in partial recovery of glymphatic function [123], further reinforcing its importance in the therapeutic landscape of stroke.
2.7. Traumatic Brain Injury (TBI)
Widespread and persistent disruption of glymphatic system function has been demonstrated in several experimental models of TBI, characterized by impaired CSF influx and efflux very shortly post-injury [124]. This disruption could endure up to 10 weeks in adult mild TBI models particularly in areas such as the olfactory bulb [125,126]. Disruption of normal brain efflux kinetics is further supported by the reduced drainage to the cervical lymph nodes [124]. Glymphatic impairment was linked to loss of motor coordination and balance deficits. Mechanistically, increased noradrenaline levels released due to post-traumatic sympathetic overactivation seem to contribute to the stagnation of glymphatic flow by suppressing vessel contractility, leading to edema and impaired debris clearance [127].
Deregulation of clearance has been associated with alterations in AQP4 expression and polarization [128,129]. However, the role of AQP4 seems to be quite complex. Reduced AQP4 expression is reported in posterior cortical regions and the ventral cortex [124] although other reports have noticed the upregulation of the global AQP4 expression even if depolarized [130,131]. Deficiency of AQP4 expression and loss of astrocytic polarization was directly linked to impaired solute clearance leading to phosphorylated tau (P-tau) accumulation in both the contralateral and ipsilateral hemispheres, exacerbated neurodegeneration and cognitive deficits [132]. On the other hand, small interfering RNA-mediated inhibition of AQP4 significantly reduced brain edema in the acute phase post-TBI (6 to 12 hours) [133]. Temporal patterns of AQP4 expression post-TBI provide further insights into this controversy. Levels of AQP4 seem to peak early during the acute phase (12 and 72 hours post-TBI) and decline later (by day 15) [130]. These changes are closely associated with the volume of brain water content and the severity of the edema. Notably, although AQP4 has an important role in edema formation, in the long-term its function is compensatory assisting in its resolution once the BBB stability has been restored [131]. However, others have noticed the emergence of glymphatic clearance dysfunction around 28 days post-injury in a blast mild TBI model [129].
Across studies of mild TBI (mTBI), subacute TBI, and chronic TBI, glymphatic function was assessed using the DTI-ALPS index and the estimation of ePVS burden. A consistent impairment of glymphatic function was reported [134,135,136,137]. Reduced DTI-ALPS index correlated with decline in cognitive performance [135] including verbal memory, attention, and executive function [134]. Of note, the DTI-ALPS index may have a prognostic utilization for identifying chronic cognitive impairment following TBI [26], while the cognitive decline was not related to factors reflecting clinical burden at the baseline [135]. Collectively, these findings provide cues considering a link between the DTI-ALPS index and cognitive decline that relies predominantly in glymphatic function.
Alongside reduced DTI-ALPS values, patients with mTBI had profound global white matter damage [134]. Global white matter damage partially mediated the association between the DTI-ALPS index and cognition. Furthermore, the DTI-ALPS index was negatively correlated with plasma neurofilament light (NfL) expression, linking reduced DTI-ALPS to the severity of axonal damage biology [137]. These observations suggest that impaired glymphatic activity is present in more severe or diffuse injury phenotypes [134,136,137] pointing towards a relationship between glymphatic dysfunction and diffuse white-matter integrity to explain cognitive deficits after mTBI [134].
On the other hand, reactive glymphatic hyperactivity has also been reported to occur post-injury. Higher DTI-ALPS index in mTBI compared to non-injured subjects, including MRI-negative mTBI patients [138] has been reported. A gradual increase of the DTI-ALPS index from the acute (14 days post-injury) to the chronic phase (6–12 months post-injury) [26] was noticed. These observations may reflect a dynamic regulation of glymphatic activity in turn of neuronal damage and the activation of a compensatory clearance pathway working towards partial recovery. This is supported by improvements in sleep quality that are associated with glymphatic hyperactivity [26]. Additionally, these dynamic fluctuations of glymphatic activity in TBI renders the DTI-ALPS index as a very useful marker in interpreting the correlation between time- and context-dependent shifts in perivascular diffusivity and clinical outcomes.
Collectively, these studies reinforce the growing understanding that glymphatic dysfunction and AQP4, particularly, play a significant role in TBI pathophysiology. Chronic impairment of glymphatic function post TBI may render post-traumatic brain prone to the accumulation of neurotoxic proteins that lead to neurodegeneration [132]. This is supported by the restoration of the glymphatic function exerted by some of the therapeutic strategies applied in experimental models such as Omega-3 polyunsaturated fatty acids [139], adrenergic blockers [127] and GLP-1R agonists [140] which are associated with BBB preservation, improvement of neurological outcomes and reduced accumulation of inflammatory components.
2.8. Amyotrophic Lateral Sclerosis (ALS)
Studies in transgenic animals expressing mutated human superoxide dismutase (SOD) 1, that mimics ALS pathogenesis, have revealed broad changes in astrocytes homeostasis; deregulated expression of AQP4 was accompanied by depolarization [141]. These pathological features were suggested to have contributed to earlier disease onset [142] potentially due to altered CSF dynamics [143]. Glymphatic system dysfunction during early stages of ALS is further supported by a study in transgenic mice expressing cytoplasmic human TDP-43 (hTDP-43ΔNLS) under the control of doxycycline [144]. Following the cessation of doxycycline feeding, clearance of an MR agent (Magnevist) was evaluated using dynamic contrast-enhanced MRI. Altered glymphatic function was observed in transgenic mice three weeks after doxycycline withdrawal, indicating disruption at a relatively early stage in the neurodegenerative process, estimated to begin around four weeks. Subsequently, transgenic mice exhibited signs of progressive neurodegeneration in the primary motor cortex, the primary somatosensory cortex and the corticospinal tract [144].
Across recent human ALS studies, glymphatic function has been assessed using non-contrast MRI biomarkers, most commonly DTI-ALPS and estimation of choroid plexus volume fraction. Multiple datasets demonstrate lower DTI-ALPS index in patients with ALS compared to age- and sex-matched healthy individuals [145,146,147,148] and patients with other motor neuron diseases [149], consistent with impaired perivascular water diffusivity. A longitudinal study confirmed that the glymphatic impairment could be a permanent phenomenon, lasting up to 8 months [149]. Interestingly, similar to stroke, unilateral lowered DTI-ALPS index has been reported, with the right-side being significantly reduced in ALS patients compared to healthy individuals, while the left side was not affected [147]. These observations demonstrate that glymphatic impairment may contribute substantially to neuronal damage in ALS in a unique manner.
Clinical and demographic factors affect glymphatic activity in ALS patients. The DTI-ALPS index has been shown to decline with advancing age [147,149] while choroid plexus volume fraction is also age-associated [146] potentially linking aging with vulnerability to ALS pathology due to gradually impaired glymphatic system. Alternatively, increased choroid plexus volumes may represent compensatory CSF production due to reduced waste clearance [146]. Moreover, female ALS patients were shown to have higher mean DTI-ALPS values compared to their male counterparts [147]. Positive association with metrics of clinical disability [148,149] reflecting sensorimotor dysfunction and disease duration [145] has been also reported, suggestive of a link between glymphatic and functional neural impairment with disease severity. However, others found no correlation with King’s stage, cognitive function questionnaires and other clinical parameters [146,147]. Last, glymphatic dysfunction in ALS patients has been associated with sleep disturbances [148].
Collectively, glymphatic impairment in early stages of ALS pathogenesis may substantially contribute to the disease burden. Therefore, clinical assessment of glymphatic function could potentially provide cues for designing a better therapeutic approach earlier in the disease course.
3. Inflammaging
Enhanced depolarization of AQP4 as well as altered CSF dynamics point towards a deregulation of glymphatic system during aging. Increased expression of AQP4 with advancing age has been detected in human and mice [150,151]. Staining patterns of AQP4 in old, non-demented individuals shows a distinct diffuse parenchymal pattern compared to the perivascular polarization observed in younger individuals. Enlarged PVS and increased water pool is also observed in aging brains [152] pointing towards a reduction in the CSF turnover [10] and impediment of CSF flow [153]. Besides impaired glymphatic flow, draining to meningeal lymphatic vessels was found also to be related to aging in patients undergoing 3-dimensional T1-weighted imaging following intrathecal injection of gadolinium [154]. These observations suggest a holistic glymphatic flow stagnation in aged individuals and related experimental models.
Although limited, evidence points towards an association between glymphatic impairment and aging that leads to neuroinflammatory conditions. The presence of excessive immune cells in PVS due to chronic low-grade inflammation [155] as well as the reduced arterial pulsatility [12] could explain mechanistically the reduced CSF flow. Immune-mediated loss of meningeal drainage capacity has been observed in old mice [156]. Moreover, a substantial decline in the fluid exchange between CSF and the brain parenchyma in mice of advanced age (18 months old) compared to younger ones (2-3 months old) was accompanied by reduced clearance of injected Aβ and loss of perivascular polarization of AQP4 [8]. Of interest was that AQP4 was found to be localized in the areas that affect the recirculation of CSF into and through the brain interstitium while its expression was elevated in areas where the penetration of CSF tracer was reduced, such as the pial surface. Depolarization of AQP4 is also associated with age-related cognitive decline and increased Aβ burden [28], suggesting AQP4-dependent cognitive deterioration. Although these are preliminary evidence, a feedback loop could be suggested: chronic inflammation leads to the accumulation of immune mediators within CNS hampering the glymphatic function that subsequently fosters protein aggregation resulting in enhanced neuroinflammation and further obstruction of glymphatic flow (Figure 2). This theoretical mechanism could thus contribute to the onset of neurocognitive and neurodegenerative conditions.
4. Gut-Brain Axis
Recent evidence points to a possible interplay between the gut-brain inflammatory axis and the dysfunction of the glymphatic system within CNS. Indirect effects of gut dysbiosis may have an impact in the glymphatic function via several mechanisms [157]. Particularly, gut dysbiosis may result in the accumulation of pro-inflammatory mediators in the periphery as well as the activation of peripheral immune cells. Following their migration within CNS, signaling effects in local glial cells may enhance the neuroinflammatory burden that has the potential to halt the glymphatic flow [5]. Besides blood circulation, additional routes, such as the vagus nerve, allow for direct communication between the gut and the brain thus enabling the local build-up of inflammation that may result in the aggregation of neurotoxic peptides via a feedback loop [158]. Moreover, gut microbiota regulates the release of neurotransmitters and neuroactive hormones that may perturb astrocytic functions rendering them incapable for eliciting their role in the regulation of glymphatic flow and waste clearance [159]. Gut dysbiosis may also lead to dysregulation of BBB integrity through the release of short-chain fatty acids [160]. Given that BBB is suspected to serve as a complementary mechanism to the glymphatic system [161], its dysregulation can compromise the waste removal machinery. The composition of gut microbiota is further associated with the regulation of circadian rhythms, which are directly related to the activity of the glymphatic system. Indeed, microbiota dysbiosis may generate potent activators of aryl hydrocarbon receptors which are able to disrupt circadian rhythms via sleep fragmentation [162] and subsequently impair glymphatic flow [163].
We can further speculate on the possible role of gut dysbiosis in the aggregation of neurotoxic proteins within the CNS focusing on studies that employ a gut-targeted modification of microflora. Gut dysbiosis induced by administration of periodontal pathogen in mice has been shown to be associated with increased Aβ accumulation alongside systemic and focal CNS inflammation and reactive astrogliosis [164]. Additionally, dextran sodium sulfate-induced colitis in aged mice led to extended gut inflammation that was accompanied by increased astrogliosis, impaired glymphatic clearance, depolarization of AQP4 and increased Aβ accumulation [165]. In this specific experimental model, glymphatic function was restored and neuroinflammation was mitigated following pharmacological inhibition of the NLRP3 inflammasome suggesting an interconnectedness of gut-induced neuroinflammation and glymphatic dysfunction.
Existing evidence points towards a hypothetic mechanistic interplay between secreted metabolites by the gut and CNS homeostasis, with waste clearance within the CNS being one of the domains affected (Figure 2). However, more research is warranted to confirm that this existing interaction may lead to the deregulation of waste clearance from the brain.
5. Regulation of Glymphatic Function
5.1. Sleep
Injected trackers in the cisterna magna or the choroid plexus have yielded initial findings supporting that clearance of solutes from the brain is accelerated in either natural sleeping or anesthetized mice compared to awake mice while sleep deprivation led to reduced CSF influx [166,167]. Increased CSF influx is proposed to occur due to the expansion of ISF volume, thus facilitating the fluid interchange [168]. Furthermore, sleep fragmentation induced via tilting platforms in 5X FAD mice resulted in compromised short-term and spatial memory accompanied by increased accumulation of Aβ and astrogliosis [169]. The expression of AQP4 was deregulated both in wild type and 5X FAD mice following sleep deprivation suggesting that dysfunction in the glymphatic system may be associated with cognitive deficits.
Using the DTI-ALPS index, Saito and colleagues have recently shown that glymphatic activity was significantly lower in a group of patients with sleep disruption compared to individuals with normal sleep [170]. Furthermore, impaired glymphatic function has been demonstrated in patients with obstructive sleep apnea [171]. Altered glymphatic function has been further correlated with chronic sleep disturbance in patients with iNPH compared to non-demented individuals [172].
Altogether, these findings support the existing hypothesis that adequate sleep keeps the glymphatic flow active maintaining brain homeostasis. Of note, sleep disturbances have been associated with behavioral disturbances in PD patients [173], tau accumulation and faster cognitive deterioration in AD patients [174]. Enhanced vasomotion during sleep may be the key mechanism for explaining sleep-mediated glymphatic clearance enhancement [175], although additional research is warranted to unravel the pathways involved.
Anesthesia
Anesthetic state seems to influence glymphatic function through its effects on neural oscillations, vascular pulsatility, and adrenergic tone. Rodents anesthetized with ketamine/xylazine show higher CSF tracer influx into the brain compared to mice under isoflurane alone or other agents [176]. It is not clear though whether elevated CSF influx depends on the increased CSF production, since contradictory results have been published [177,178]. Enhanced influx is coupled to the induction of slow-wave electroencephalogram activity, which promotes low noradrenergic signaling and synchronized neuronal activity that widens perivascular spaces, thereby facilitating CSF-ISF exchange. In contrast, anesthetics such as isoflurane, which generate lighter sedation with higher heart rates and less delta power, do not have a substantial impact on glymphatic transport. Thus, deeper slow-wave oscillatory activity under certain anesthetics appears to facilitate perivascular CSF entry into the parenchyma.
Structural changes following anesthesia also confer to altered glymphatic function. Prolonged or high-dose isoflurane disrupts AQP4 localization, impairing solute efflux and leading to accumulation of inflammatory proteins and Aβ, phenomena associated with postoperative cognitive decline [179]. Restoration of AQP4 polarization could preserve partially waste clearance and neurocognitive performance. Further, co-administration of dexmedetomidine, an α2-adrenergic agonist that reduces locus coeruleus activity, with low-dose isoflurane enhances glymphatic transport compared to isoflurane alone, pointing towards a dependency on the noradrenergic tone and vascular dynamics [180].
These findings underscore a two-sided effect of anesthesia: when high-dose isoflurane is administered or during prolonged exposure, glymphatic function may be stalled, while the usage of anesthetics that promote slow-wave neuronal states leads to maintenance of vascular pulsatility and AQP4 polarization. Reduced adrenergic signaling results in relaxed perivascular spaces and expansion of interstitial spaces [166] that subsequently lowers vascular resistance, thus promoting clearance [180].
Body Posture
Changes in posture may have an impact on CSF circulation [181]. Furthermore, CSF pressure and volume are influenced by posture due to gravity [182]. This is crucial since elevated intracranial pressure has been implicated in several neurodegenerative conditions [183]. Additionally, postoperative cognitive impairment has been associated with the acquired posture during surgery [184]. These findings suggest an interplay between the body posture and altered CSF dynamics that may have an impact on brain functions.
Using MRI and fluorescence tracers in rodents, researchers have shown that Aβ clearance is significantly superior in the lateral position compared to the supine or prone positions suggesting the existence of an evolved mechanism to sustain brain homeostatic glymphatic function [185]. Similar, in human subjects the CSF exchange seems to be enhanced in supine compared to the upright position, providing benefits for brain waste clearance processes [186]. Supine position seems to be ideal for the glymphatic process possibly by increasing the intracranial pressure which subsequently allows for more CSF movements and higher driving pressure [187]. More insights concerning the relationship between body posture and glymphatic function are warranted to elucidate the mechanisms involved.
Alcohol
Alcohol intake has been shown to exert dose-dependent and temporally distinct effects on glymphatic function. Acute and chronic exposure to high levels of ethanol (>1.5 g/kg) significantly suppresses glymphatic transport, leading to impaired CSF influx and reduced clearance of waste metabolites [188,189]. Suppression is associated with astrogliosis, AQP4 depolarization, and reduced cerebrovascular pulsatility thus contributing to compromised Aβ clearance [189]. By contrast, low-dose ethanol exposure (0.5 g/kg) appears to enhance glymphatic activity which is accompanied by reduced GFAP expression and stabilization of AQP4 polarization [188]. Furthermore, in humans, acute moderate alcohol administration induces reversible ventricular enlargement possibly reflecting a shift in CSF dynamics and water volume suggesting a glymphatic system malfunction [190].
Mechanistically, ethanol-induced vasodilation following low exposure to alcohol may enhance vascular reactivity, thereby promoting perivascular clearance of larger solutes and proteins [191]. Higher volumes of alcohol may have a detrimental effect inducing astrocytic amyloid generation and enhanced astrogliosis [192] as well as in vivo depolarization of AQP4 [193]. Increased astrogliosis was also present in human postmortem studies of patients with alcohol use disorder [194].
Collectively, these observations suggest that alcohol modulates glymphatic clearance in a dose-dependent manner. Low-dose ethanol may transiently enhance waste clearance through increased vascular pulsatility, whereas chronic or high-dose exposure results in glymphatic flow stagnation. An overall of lifestyle modulators is depicted in Figure 2.
6. Conclusions
The evidence synthesized in this review provides available data that supports that glymphatic system dysfunction may constitute a common clinically relevant feature across neurodegenerative and neuroinflammatory conditions. However, it is not clear whether glymphatic dysfunction is a mechanism preceding neurodegeneration or is an epiphenomenon of underlying pathogenesis. Dysfunction appears as a vulnerability that links aging, inflammation and neurodegeneration. More importantly, glymphatic dysfunction seems to be detectable in prodromal and early-stage disease phenotypes implying that a waste clearance deterioration may precede initial stages of disease pathogenesis. These findings converge on the notion that glymphatic dysfunction may be among the drivers of disease onset. Therefore, we cannot make concrete conclusions considering the potential role of glymphatic system while we highlight the need for future experiments that will decipher this experimental void in our knowledge.
Altered brain homeostasis due to the impaired glymphatic flow appears potentially to lead to CNS function deficits, including cognitive decline among others. Cognitive deficits dominate findings of human imaging studies indicating a sensitivity of brain regions, such as the hippocampus and temporal cortex, in the accumulated waste [195]. Furthermore, the consistency of glymphatic deregulation among different diseases of the CNS argues for a shared upstream mechanism rather than a disease-specific process. With respect to all domains that need to be validated, waste clearance inability may rise as a core mechanism for neurodegeneration. Variable interplay of glymphatic system with other waste clearance pathways should be explored further to gain insights regarding different pathways of neurodegeneration [196].
Another limitation regarding pre-clinical models is the translation of experimental findings to humans due to species differences; for example humans exhibit higher anatomical complexity compared to rodents [197] while the latter higher AQP4 perivascular polarization compared to the former [198]. However, multiple evidence from human imaging studies across AD, PD, ALS, MS, FTD, stroke, and TBI, consistently demonstrate altered glymphatic function. Therefore, we believe that this issue does not fall within the limitations of this synthesis. In most human imaging studies glymphatic function has been assessed with the DTI-ALPS index which serves as a proxy. Low DTI-ALPS indices are often associated with increased perivascular space burden, and choroid plexus abnormalities. These observations support a model in which impaired clearance of aggregation-prone proteins, inflammatory mediators, and metabolic byproducts contributes to a neuroinflammatory cascade that potentially leads to neuronal dysfunction. It should be noted that the DTI-ALPS is a practical, non-invasive surrogate marker of glymphatic function; however, limitations concerning its application exist. The method assumes that diffusivity along PVS reflects glymphatic activity. Yet, diffusion anisotropy may also be influenced by other factors including white matter microstructure, axonal degeneration, edema, or small vessel disease, potentially confounding interpretation of outcomes [199]. Moreover, DTI-ALPS index is a snapshot of water diffusivity, and not representative of dynamic flow. Therefore, its application can be influenced by diffusion as well as convective flow, which is a lively debate concerning glymphatic biology [200]. Lack of established outputs as well as variability of monitoring methods may also reduce variability until a consensus is reached. Thus, although DTI-ALPS is a promising clinical tool, its outcomes should be interpreted with caution and in combination with other endpoints to properly assess glymphatic function in clinical routine. Future experiments should be focused on the functional improvement of DTI-ALPS as well as the development of robust and reliable diagnostic markers for the assessment of glymphatic capacity in humans.
Glymphatic function seems to be strongly dependent on the function of AQP4. Through our synthesis the role of AQP4 is framed as a central facilitator of glymphatic transport due to its polarized expression at astrocytic perivascular endfeet. Initial experiments using Aqp4 knockout mice have supported this mechanistic link [1]. However, subsequent studies employing models of Aqp4 deletion have questioned its role in the magnitude of parenchymal tracer spread [201]. Additionally, others have supported those technical issues such as the type of anesthesia used, and the timing as well as the tracer delivery route may influence our understanding of the role of AQP4 [202]. Thus, while AQP4 likely enhances perivascular CSF–ISF exchange by increasing astrocytic water permeability, whether it is essential for large-scale convective glymphatic flow or instead modulates local mixing and dispersion remains unresolved.
Age-associated structural changes in the vascular integrity, alterations in astrocytes physiology with prominent AQP4 depolarization and systemic inflammation caused by gut dysbiosis may result in gradually accumulated inflammatory burden and loss of BBB integrity. Glymphatic dysfunction driven by aging, alongside these background conditions may render the CNS environment vulnerable for neurodegeneration onset. This bidirectional interaction suggests that inflammaging and glymphatic failure work in parallel, providing a theoretical mechanism for explanation of the strong age-dependent risk of progression of neurodegeneration. Within this model, glymphatic dysfunction may result in retention of immunogenic components thus amplifying inflammatory signaling, thereby accelerating pathogenic cascades. In the opposite direction, accumulated inflammatory burden may result in glymphatic efflux stagnation further enhancing the presence of toxic metabolic byproducts and aggregation-prone proteins that cause neuronal damage.
7. Future Directions
Collectively, imaging evidence positions monitoring of glymphatic function as a promising and powerful accessory tool for clinical management of patients with neurodegenerative diseases [2]. Development of biomarkers based on non-invasive MRI-based methods, particularly DTI-ALPS, may offer robust and widespread longitudinal options for the assessment of brain clearance function. Further standardization of acquisition and analysis protocols, as well as the establishment of a consensus among physicians considering normative reference ranges, and assessment of treatment response would entitle the implementation of glymphatic system in the armamentarium of neurologists. This way earlier detection of brain vulnerabilities and risk stratification-based prognosis could thus be enabled. From a therapeutic perspective, therapeutic strategies for enhancing glymphatic clearance could include interventions that improve sleep quality, reduce systemic and CNS inflammation burden and preserve the established astrocytes interactions and AQP4 polarization. Eventually, harnessing the modalities of the glymphatic system could open the path for the development and repurposing of cross-disease therapeutic strategies given its involvement in multiple neurodegenerative pathways.
Author Contributions
Conceptualization, K.I.V.; writing—original draft preparation, K.I.V. and S.T.; writing—review and editing, K.I.V., N.S.T., E.S., G.N.P., C.L., S.T.; visualization, G.N.P.; supervision, K.I.V. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Data Availability Statement
No new data were generated through this study.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| Aβ | Amyloid-beta |
| AD | Alzheimer's disease |
| ALS | Amyotrophic lateral sclerosis |
| ALPS | Analysis Along the Perivascular Space |
| AQP4 | Aquaporin-4 |
| APP/PS1 | Amyloid precursor protein/Presenilin-1 |
| BBB | Blood-brain barrier |
| bvFTD | Behavioral variant frontotemporal dementia |
| CNS | Central nervous system |
| CSF | Cerebrospinal fluid |
| CSVD | Cerebral small vessel disease |
| DTI | Diffusion tensor imaging |
| DTI-ALPS | Diffusion tensor imaging along the perivascular space |
| EAE | Experimental autoimmune encephalomyelitis |
| ePVS | Enlarged perivascular spaces |
| FTD | Frontotemporal dementia |
| GFAP | Glial fibrillary acidic protein |
| GLP-1R | Glucagon-like peptide-1 receptor |
| ICH | Intracerebral hemorrhage |
| iNPH | Idiopathic normal pressure hydrocephalus |
| ISF | Interstitial fluid |
| MCAO | Middle cerebral artery occlusion |
| MCI | Mild cognitive impairment |
| MMSE | Mini-Mental State Examination |
| MoCA | Montreal Cognitive Assessment |
| FTD | Frontotemporal dementia |
| GFAP | Glial fibrillary acidic protein |
| GLP-1R | Glucagon-like peptide-1 receptor |
| ICH | Intracerebral hemorrhage |
| iNPH | Idiopathic normal pressure hydrocephalus |
| ISF | Interstitial fluid |
| MCAO | Middle cerebral artery occlusion |
| MCI | Mild cognitive impairment |
| MMSE | Mini-Mental State Examination |
| MoCA | Montreal Cognitive Assessment |
| MOG | Myelin oligodendrocyte glycoprotein |
| MRI | Magnetic resonance imaging |
| MS | Multiple sclerosis |
| NfL | Neurofilament light |
| NLRP3 | NOD-, LRR- and pyrin domain-containing protein 3 |
| PD | Parkinson's disease |
| PFFs | Preformed fibrils |
| PVS | Perivascular spaces |
| SAH | Subarachnoid hemorrhage |
| SCD | Subjective cognitive decline |
| SNCA | Alpha-synuclein (gene/protein) |
| SOD1 | Superoxide dismutase 1 |
| TBI | Traumatic brain injury |
| TDP-43 | TAR DNA-binding protein 43 |
| UPDRS | Unified Parkinson's Disease Rating Scale |
| VCID | Vascular cognitive impairment and dementia |
| VTN | Ventral thalamic nucleus |
| 5XFAD | Five familial Alzheimer's disease transgenic mouse model |
References
- Iliff JJ, Wang M, Liao Y, Plogg BA, Peng W, Gundersen GA, et al. A paravascular pathway facilitates CSF flow through the brain parenchyma and the clearance of interstitial solutes, including amyloid beta. Sci Transl Med. 2012;4(147):147ra11. [CrossRef]
- Voumvourakis K, Thomaidis NS, Tsiodras S. Mapping the Brain's Glymphatic System. Biomedicines. 2026;14(2). [CrossRef]
- Klostranec JM, Vucevic D, Bhatia KD, Kortman HGJ, Krings T, Murphy KP, et al. Current Concepts in Intracranial Interstitial Fluid Transport and the Glymphatic System: Part I-Anatomy and Physiology. Radiology. 2021;301(3):502-14. [CrossRef]
- Ding Z, Fan X, Zhang Y, Yao M, Wang G, Dong Y, et al. The glymphatic system: a new perspective on brain diseases. Front Aging Neurosci. 2023;15:1179988. [CrossRef]
- Zou K, Deng Q, Zhang H, Huang C. Glymphatic system: a gateway for neuroinflammation. Neural Regen Res. 2024;19(12):2661-72. [CrossRef]
- Ishida K, Yamada K, Nishiyama R, Hashimoto T, Nishida I, Abe Y, et al. Glymphatic system clears extracellular tau and protects from tau aggregation and neurodegeneration. J Exp Med. 2022;219(3). [CrossRef]
- Zhang Y, Zhang C, He XZ, Li ZH, Meng JC, Mao RT, et al. Interaction Between the Glymphatic System and alpha-Synuclein in Parkinson's Disease. Mol Neurobiol. 2023;60(4):2209-22. [CrossRef]
- Kress BT, Iliff JJ, Xia M, Wang M, Wei HS, Zeppenfeld D, et al. Impairment of paravascular clearance pathways in the aging brain. Ann Neurol. 2014;76(6):845-61. [CrossRef]
- Herzog MJ, Muller P, Lechner K, Stiebler M, Arndt P, Kunz M, et al. Arterial stiffness and vascular aging: mechanisms, prevention, and therapy. Signal Transduct Target Ther. 2025;10(1):282. [CrossRef]
- Smets NG, Strijkers GJ, Vinje V, Bakker E. Cerebrospinal fluid turnover as a driver of brain clearance. NMR Biomed. 2024;37(7):e5029. [CrossRef]
- Voumvourakis KI, Sideri E, Papadimitropoulos GN, Tsantzali I, Hewlett P, Kitsos D, et al. The Dynamic Relationship between the Glymphatic System, Aging, Memory, and Sleep. Biomedicines. 2023;11(8). [CrossRef]
- Stoquart-ElSankari S, Baledent O, Gondry-Jouet C, Makki M, Godefroy O, Meyer ME. Aging effects on cerebral blood and cerebrospinal fluid flows. J Cereb Blood Flow Metab. 2007;27(9):1563-72. [CrossRef]
- Palmer AL, Ousman SS. Astrocytes and Aging. Front Aging Neurosci. 2018;10:337. [CrossRef]
- Alavian F, Hajimohammadi A. Interplay between gut Microbiome and glymphatic system in cognitive function and memory regulation. Mol Biol Rep. 2025;52(1):1038. [CrossRef]
- Camberos-Barraza J, Camacho-Zamora A, Batiz-Beltran JC, Osuna-Ramos JF, Rabago-Monzon AR, Valdez-Flores MA, et al. Sleep, Glial Function, and the Endocannabinoid System: Implications for Neuroinflammation and Sleep Disorders. Int J Mol Sci. 2024;25(6). [CrossRef]
- Bao C, Luo H, Wang J, Liu X, Li Y, Yang J, et al. Poor glymphatic function is associated with mild cognitive impairment and its progression to Alzheimer's disease: A DTI-ALPS study. J Prev Alzheimers Dis. 2025;12(7):100156. [CrossRef]
- Carotenuto A, Cacciaguerra L, Pagani E, Preziosa P, Filippi M, Rocca MA. Glymphatic system impairment in multiple sclerosis: relation with brain damage and disability. Brain. 2022;145(8):2785-95. [CrossRef]
- Harrison IF, Ismail O, Machhada A, Colgan N, Ohene Y, Nahavandi P, et al. Impaired glymphatic function and clearance of tau in an Alzheimer's disease model. Brain. 2020;143(8):2576-93. [CrossRef]
- Kamagata K, Andica C, Takabayashi K, Saito Y, Taoka T, Nozaki H, et al. Association of MRI Indices of Glymphatic System With Amyloid Deposition and Cognition in Mild Cognitive Impairment and Alzheimer Disease. Neurology. 2022;99(24):e2648-e60. [CrossRef]
- Li Y, Wang L, Zhong J, Xu H, Han Y, Alzheimer's Disease Neuroimaging I, et al. Impaired glymphatic function as a biomarker for subjective cognitive decline: An exploratory dual cohort study. Alzheimers Dement. 2024;20(9):6542-55. [CrossRef]
- Lin B, Leong YY, Mohamad M. DTI-ALPS index as a predictor of glymphatic system dysfunction in cerebral infarction. Am J Transl Res. 2025;17(6):4306-14. [CrossRef]
- Premi E, Diano M, Mattioli I, Altomare D, Cantoni V, Bocchetta M, et al. Impaired glymphatic system in genetic frontotemporal dementia: a GENFI study. Brain Commun. 2024;6(4):fcae185. [CrossRef]
- Ren J, Xie D, Wang L, Wu Z, Lin S, Jin Q, et al. Glymphatic system dysfunction as a biomarker of disease progression in Parkinson's disease: neuroimaging evidence from longitudinal cohort studies. J Neurol. 2025;272(3):196. [CrossRef]
- Ayyappan K, Unger L, Kitchen P, Bill RM, Salman MM. Measuring glymphatic function: Assessing the toolkit. Neural Regen Res. 2026;21(2):534-41. [CrossRef]
- Keil SA, Jansson D, Braun M, Iliff JJ. Glymphatic dysfunction in Alzheimer's disease: A critical appraisal. Science. 2025;389(6756):eadv8269. [CrossRef]
- Zhuo J, Raghavan P, Li J, Roys S, Njonkou Tchoquessi RL, Chen H, et al. Longitudinal assessment of glymphatic changes following mild traumatic brain injury: Insights from perivascular space burden and DTI-ALPS imaging. Front Neurol. 2024;15:1443496. [CrossRef]
- Bergsland N, Dwyer MG, Jakimovski D, Tavazzi E, Weinstock-Guttman B, Zivadinov R. Choroid plexus enlargement is associated with future periventricular neurodegeneration in multiple sclerosis. Mult Scler Relat Disord. 2024;87:105668. [CrossRef]
- Zeppenfeld DM, Simon M, Haswell JD, D'Abreo D, Murchison C, Quinn JF, et al. Association of Perivascular Localization of Aquaporin-4 With Cognition and Alzheimer Disease in Aging Brains. JAMA Neurol. 2017;74(1):91-9. [CrossRef]
- Pedersen TJ, Keil SA, Han W, Wang MX, Iliff JJ. The effect of aquaporin-4 mis-localization on Abeta deposition in mice. Neurobiol Dis. 2023;181:106100. [CrossRef]
- Simon M, Wang MX, Ismail O, Braun M, Schindler AG, Reemmer J, et al. Loss of perivascular aquaporin-4 localization impairs glymphatic exchange and promotes amyloid beta plaque formation in mice. Alzheimers Res Ther. 2022;14(1):59. [CrossRef]
- Burfeind KG, Murchison CF, Westaway SK, Simon MJ, Erten-Lyons D, Kaye JA, et al. The effects of noncoding aquaporin-4 single-nucleotide polymorphisms on cognition and functional progression of Alzheimer's disease. Alzheimers Dement (N Y). 2017;3(3):348-59. [CrossRef]
- Chandra A, Farrell C, Wilson H, Dervenoulas G, De Natale ER, Politis M, et al. Aquaporin-4 polymorphisms predict amyloid burden and clinical outcome in the Alzheimer's disease spectrum. Neurobiol Aging. 2021;97:1-9. [CrossRef]
- Xu Z, Xiao N, Chen Y, Huang H, Marshall C, Gao J, et al. Deletion of aquaporin-4 in APP/PS1 mice exacerbates brain Abeta accumulation and memory deficits. Mol Neurodegener. 2015;10:58. [CrossRef]
- Yang W, Wu Q, Yuan C, Gao J, Xiao M, Gu M, et al. Aquaporin-4 mediates astrocyte response to beta-amyloid. Mol Cell Neurosci. 2012;49(4):406-14. [CrossRef]
- Abe Y, Ikegawa N, Yoshida K, Muramatsu K, Hattori S, Kawai K, et al. Behavioral and electrophysiological evidence for a neuroprotective role of aquaporin-4 in the 5xFAD transgenic mice model. Acta Neuropathol Commun. 2020;8(1):67. [CrossRef]
- Lopes DM, Wells JA, Ma D, Wallis L, Park D, Llewellyn SK, et al. Glymphatic inhibition exacerbates tau propagation in an Alzheimer's disease model. Alzheimers Res Ther. 2024;16(1):71. [CrossRef]
- Da Mesquita S, Louveau A, Vaccari A, Smirnov I, Cornelison RC, Kingsmore KM, et al. Functional aspects of meningeal lymphatics in ageing and Alzheimer's disease. Nature. 2018;560(7717):185-91. [CrossRef]
- Da Mesquita S, Papadopoulos Z, Dykstra T, Brase L, Farias FG, Wall M, et al. Meningeal lymphatics affect microglia responses and anti-Abeta immunotherapy. Nature. 2021;593(7858):255-60. [CrossRef]
- Feng W, Zhang Y, Wang Z, Xu H, Wu T, Marshall C, et al. Microglia prevent beta-amyloid plaque formation in the early stage of an Alzheimer's disease mouse model with suppression of glymphatic clearance. Alzheimers Res Ther. 2020;12(1):125. [CrossRef]
- Zeng Q, Li K, Luo X, Wang S, Xu X, Jiaerken Y, et al. The association of enlarged perivascular space with microglia-related inflammation and Alzheimer's pathology in cognitively normal elderly. Neurobiol Dis. 2022;170:105755. [CrossRef]
- Peng W, Achariyar TM, Li B, Liao Y, Mestre H, Hitomi E, et al. Suppression of glymphatic fluid transport in a mouse model of Alzheimer's disease. Neurobiol Dis. 2016;93:215-25. [CrossRef]
- Schirge PM, Perneczky R, Taoka T, Ruiz-Rizzo AL, Ersoezlue E, Forbrig R, et al. Perivascular space and white matter hyperintensities in Alzheimer's disease: associations with disease progression and cognitive function. Alzheimers Res Ther. 2025;17(1):62. [CrossRef]
- Huang SY, Zhang YR, Guo Y, Du J, Ren P, Wu BS, et al. Glymphatic system dysfunction predicts amyloid deposition, neurodegeneration, and clinical progression in Alzheimer's disease. Alzheimers Dement. 2024;20(5):3251-69. [CrossRef]
- Steward CE, Venkatraman VK, Lui E, Malpas CB, Ellis KA, Cyarto EV, et al. Assessment of the DTI-ALPS Parameter Along the Perivascular Space in Older Adults at Risk of Dementia. J Neuroimaging. 2021;31(3):569-78. [CrossRef]
- Zhang X, Wang Y, Jiao B, Wang Z, Shi J, Zhang Y, et al. Glymphatic system impairment in Alzheimer's disease: associations with perivascular space volume and cognitive function. Eur Radiol. 2024;34(2):1314-23. [CrossRef]
- Cullell N, Caruana G, Elias-Mas A, Delgado-Sanchez A, Artero C, Buongiorno MT, et al. Glymphatic system clearance and Alzheimer's disease risk: a CSF proteome-wide study. Alzheimers Res Ther. 2025;17(1):31. [CrossRef]
- Fan Y, Kong H, Shi X, Sun X, Ding J, Wu J, et al. Hypersensitivity of aquaporin 4-deficient mice to 1-methyl-4-phenyl-1,2,3,6-tetrahydropyrindine and astrocytic modulation. Neurobiol Aging. 2008;29(8):1226-36. [CrossRef]
- Chi Y, Fan Y, He L, Liu W, Wen X, Zhou S, et al. Novel role of aquaporin-4 in CD4+ CD25+ T regulatory cell development and severity of Parkinson's disease. Aging Cell. 2011;10(3):368-82. [CrossRef]
- Zhang J, Yang B, Sun H, Zhou Y, Liu M, Ding J, et al. Aquaporin-4 deficiency diminishes the differential degeneration of midbrain dopaminergic neurons in experimental Parkinson's disease. Neurosci Lett. 2016;614:7-15. [CrossRef]
- Fang Y, Dai S, Jin C, Si X, Gu L, Song Z, et al. Aquaporin-4 Polymorphisms Are Associated With Cognitive Performance in Parkinson's Disease. Front Aging Neurosci. 2021;13:740491. [CrossRef]
- Cui H, Wang W, Zheng X, Xia D, Liu H, Qin C, et al. Decreased AQP4 Expression Aggravates a-Synuclein Pathology in Parkinson's Disease Mice, Possibly via Impaired Glymphatic Clearance. J Mol Neurosci. 2021;71(12):2500-13. [CrossRef]
- Zou W, Pu T, Feng W, Lu M, Zheng Y, Du R, et al. Blocking meningeal lymphatic drainage aggravates Parkinson's disease-like pathology in mice overexpressing mutated alpha-synuclein. Transl Neurodegener. 2019;8:7. [CrossRef]
- Gu XL, Long CX, Sun L, Xie C, Lin X, Cai H. Astrocytic expression of Parkinson's disease-related A53T alpha-synuclein causes neurodegeneration in mice. Mol Brain. 2010;3:12. [CrossRef]
- Zhao Y, Xu C, Chen Y, Gong T, Zhuo M, Zhao C, et al. Glymphatic dysfunction exacerbates cognitive decline by triggering cortical degeneration in Parkinson's disease: evidence from diffusion-tensor MRI. Brain Commun. 2025;7(1):fcaf029. [CrossRef]
- Yao J, Huang T, Tian Y, Zhao H, Li R, Yin X, et al. Early detection of dopaminergic dysfunction and glymphatic system impairment in Parkinson's disease. Parkinsonism Relat Disord. 2024;127:107089. [CrossRef]
- Cai X, Chen Z, He C, Zhang P, Nie K, Qiu Y, et al. Diffusion along perivascular spaces provides evidence interlinking compromised glymphatic function with aging in Parkinson's disease. CNS Neurosci Ther. 2023;29(1):111-21. [CrossRef]
- Bae YJ, Kim JM, Choi BS, Choi JH, Ryoo N, Song YS, et al. Glymphatic function assessment in Parkinson's disease using diffusion tensor image analysis along the perivascular space. Parkinsonism Relat Disord. 2023;114:105767. [CrossRef]
- Si X, Guo T, Wang Z, Fang Y, Gu L, Cao L, et al. Neuroimaging evidence of glymphatic system dysfunction in possible REM sleep behavior disorder and Parkinson's disease. NPJ Parkinsons Dis. 2022;8(1):54. [CrossRef]
- Zhou C, Jiang X, Guan X, Guo T, Wu J, Wu H, et al. Glymphatic system dysfunction and risk of clinical milestones in patients with Parkinson disease. Eur J Neurol. 2024;31(12):e16521. [CrossRef]
- Lind-Holm Mogensen F, Seibler P, Grunewald A, Michelucci A. Microglial dynamics and neuroinflammation in prodromal and early Parkinson's disease. J Neuroinflammation. 2025;22(1):136. [CrossRef]
- Mann DMA, Snowden JS. Frontotemporal lobar degeneration: Pathogenesis, pathology and pathways to phenotype. Brain Pathol. 2017;27(6):723-36. [CrossRef]
- Ravanidis S, Kattan FG, Doxakis E. Unraveling the Pathways to Neuronal Homeostasis and Disease: Mechanistic Insights into the Role of RNA-Binding Proteins and Associated Factors. Int J Mol Sci. 2018;19(8). [CrossRef]
- Ravanidis S, Doxakis E. RNA-Binding Proteins Implicated in Mitochondrial Damage and Mitophagy. Front Cell Dev Biol. 2020;8:372. [CrossRef]
- Nassar BR, Lippa CF. Idiopathic Normal Pressure Hydrocephalus: A Review for General Practitioners. Gerontol Geriatr Med. 2016;2:2333721416643702. [CrossRef]
- Venkat P, Chopp M, Zacharek A, Cui C, Zhang L, Li Q, et al. White matter damage and glymphatic dysfunction in a model of vascular dementia in rats with no prior vascular pathologies. Neurobiol Aging. 2017;50:96-106. [CrossRef]
- Sudduth TL, Weekman EM, Price BR, Gooch JL, Woolums A, Norris CM, et al. Time-course of glial changes in the hyperhomocysteinemia model of vascular cognitive impairment and dementia (VCID). Neuroscience. 2017;341:42-51. [CrossRef]
- Denver P, D'Adamo H, Hu S, Zuo X, Zhu C, Okuma C, et al. A Novel Model of Mixed Vascular Dementia Incorporating Hypertension in a Rat Model of Alzheimer's Disease. Front Physiol. 2019;10:1269. [CrossRef]
- Wang M, Iliff JJ, Liao Y, Chen MJ, Shinseki MS, Venkataraman A, et al. Cognitive deficits and delayed neuronal loss in a mouse model of multiple microinfarcts. J Neurosci. 2012;32(50):17948-60. [CrossRef]
- Arighi A, Arcaro M, Fumagalli GG, Carandini T, Pietroboni AM, Sacchi L, et al. Aquaporin-4 cerebrospinal fluid levels are higher in neurodegenerative dementia: looking at glymphatic system dysregulation. Alzheimers Res Ther. 2022;14(1):135. [CrossRef]
- Zhao Z, He J, Chen Y, Wang Y, Wang C, Tan C, et al. The pathogenesis of idiopathic normal pressure hydrocephalus based on the understanding of AQP1 and AQP4. Front Mol Neurosci. 2022;15:952036. [CrossRef]
- Hasan-Olive MM, Enger R, Hansson HA, Nagelhus EA, Eide PK. Loss of perivascular aquaporin-4 in idiopathic normal pressure hydrocephalus. Glia. 2019;67(1):91-100. [CrossRef]
- Jiang D, Liu L, Kong Y, Chen Z, Rosa-Neto P, Chen K, et al. Regional Glymphatic Abnormality in Behavioral Variant Frontotemporal Dementia. Ann Neurol. 2023;94(3):442-56. [CrossRef]
- Xiao D, Li J, Ren Z, Dai M, Jiang Y, Qiu T, et al. Association of cortical morphology, white matter hyperintensity, and glymphatic function in frontotemporal dementia variants. Alzheimers Dement. 2024;20(9):6045-59. [CrossRef]
- Ringstad G, Vatnehol SAS, Eide PK. Glymphatic MRI in idiopathic normal pressure hydrocephalus. Brain. 2017;140(10):2691-705. [CrossRef]
- Ringstad G, Valnes LM, Dale AM, Pripp AH, Vatnehol SS, Emblem KE, et al. Brain-wide glymphatic enhancement and clearance in humans assessed with MRI. JCI Insight. 2018;3(13). [CrossRef]
- Eide PK, Ringstad G. Delayed clearance of cerebrospinal fluid tracer from entorhinal cortex in idiopathic normal pressure hydrocephalus: A glymphatic magnetic resonance imaging study. J Cereb Blood Flow Metab. 2019;39(7):1355-68. [CrossRef]
- Rohr SO, Greiner T, Joost S, Amor S, Valk PV, Schmitz C, et al. Aquaporin-4 Expression during Toxic and Autoimmune Demyelination. Cells. 2020;9(10). [CrossRef]
- Miyamoto K, Nagaosa N, Motoyama M, Kataoka K, Kusunoki S. Upregulation of water channel aquaporin-4 in experimental autoimmune encephalomyeritis. J Neurol Sci. 2009;276(1-2):103-7. [CrossRef]
- Fournier AP, Gauberti M, Quenault A, Vivien D, Macrez R, Docagne F. Reduced spinal cord parenchymal cerebrospinal fluid circulation in experimental autoimmune encephalomyelitis. J Cereb Blood Flow Metab. 2019;39(7):1258-65. [CrossRef]
- Li L, Zhang H, Varrin-Doyer M, Zamvil SS, Verkman AS. Proinflammatory role of aquaporin-4 in autoimmune neuroinflammation. FASEB J. 2011;25(5):1556-66. [CrossRef]
- Mogensen FL, Delle C, Nedergaard M. The Glymphatic System (En)during Inflammation. Int J Mol Sci. 2021;22(14). [CrossRef]
- Preziosa P, Pagani E, Margoni M, Rubin M, Storelli L, Corazzolla G, et al. Glymphatic System May Mediate the Relation Between Choroid Plexus and Brain Damage in Multiple Sclerosis. Neurol Neuroimmunol Neuroinflamm. 2025;12(4):e200414. [CrossRef]
- Bayoumi A, Hasan KM, Thomas JA, Yazdani A, Lincoln JA. Glymphatic dysfunction in multiple sclerosis and its association with disease pathology and disability. Mult Scler. 2024;30(13):1609-19. [CrossRef]
- Rodriguez-Lorenzo S, Konings J, van der Pol S, Kamermans A, Amor S, van Horssen J, et al. Inflammation of the choroid plexus in progressive multiple sclerosis: accumulation of granulocytes and T cells. Acta Neuropathol Commun. 2020;8(1):9. [CrossRef]
- Rodriguez-Lorenzo S, Ferreira Francisco DM, Vos R, van Het Hof B, Rijnsburger M, Schroten H, et al. Altered secretory and neuroprotective function of the choroid plexus in progressive multiple sclerosis. Acta Neuropathol Commun. 2020;8(1):35. [CrossRef]
- Ricigliano VAG, Morena E, Colombi A, Tonietto M, Hamzaoui M, Poirion E, et al. Choroid Plexus Enlargement in Inflammatory Multiple Sclerosis: 3.0-T MRI and Translocator Protein PET Evaluation. Radiology. 2021;301(1):166-77. [CrossRef]
- Fleischer V, Gonzalez-Escamilla G, Ciolac D, Albrecht P, Kury P, Gruchot J, et al. Translational value of choroid plexus imaging for tracking neuroinflammation in mice and humans. Proc Natl Acad Sci U S A. 2021;118(36). [CrossRef]
- Uy CE, Binks S, Irani SR. Autoimmune encephalitis: clinical spectrum and management. Pract Neurol. 2021;21(5):412-23. [CrossRef]
- Cacciaguerra L, Yang B, Agnihotri S, Ahsan N, Fernandez K, McLeod E, et al. Frequency and Phenotype of Aquaporin-4-IgG and Coexistent Autoimmune Encephalitis Antibody Biomarkers. Neurology. 2024;103(7_Supplement_1):S104-S5. [CrossRef]
- Zhang Y, Wu D, Fan Z, Leng X, Wan T, Shi X, et al. Abnormal glymphatic system in patients with autoimmune encephalitis: Relationship with cognitive performance. Brain Res Bull. 2025;221:111232. [CrossRef]
- Zbesko JC, Nguyen TV, Yang T, Frye JB, Hussain O, Hayes M, et al. Glial scars are permeable to the neurotoxic environment of chronic stroke infarcts. Neurobiol Dis. 2018;112:63-78. [CrossRef]
- Mestre H, Du T, Sweeney AM, Liu G, Samson AJ, Peng W, et al. Cerebrospinal fluid influx drives acute ischemic tissue swelling. Science. 2020;367(6483). [CrossRef]
- Liu E, Peng X, Ma H, Zhang Y, Yang X, Zhang Y, et al. The Involvement of Aquaporin-4 in the Interstitial Fluid Drainage Impairment Following Subarachnoid Hemorrhage. Front Aging Neurosci. 2020;12:611494. [CrossRef]
- Luo C, Yao X, Li J, He B, Liu Q, Ren H, et al. Paravascular pathways contribute to vasculitis and neuroinflammation after subarachnoid hemorrhage independently of glymphatic control. Cell Death Dis. 2016;7(3):e2160. [CrossRef]
- Best JG, Barbato C, Ambler G, Du H, Banerjee G, Wilson D, et al. Association of enlarged perivascular spaces and anticoagulant-related intracranial hemorrhage. Neurology. 2020;95(16):e2192-e9. [CrossRef]
- Duperron MG, Tzourio C, Schilling S, Zhu YC, Soumare A, Mazoyer B, et al. High dilated perivascular space burden: a new MRI marker for risk of intracerebral hemorrhage. Neurobiol Aging. 2019;84:158-65. [CrossRef]
- Raposo N, Planton M, Payoux P, Peran P, Albucher JF, Calviere L, et al. Enlarged perivascular spaces and florbetapir uptake in patients with intracerebral hemorrhage. Eur J Nucl Med Mol Imaging. 2019;46(11):2339-47. [CrossRef]
- Garland P, Morton M, Zolnourian A, Durnford A, Gaastra B, Toombs J, et al. Neurofilament light predicts neurological outcome after subarachnoid haemorrhage. Brain. 2021;144(3):761-8. [CrossRef]
- Lv T, Zhao B, Hu Q, Zhang X. The Glymphatic System: A Novel Therapeutic Target for Stroke Treatment. Front Aging Neurosci. 2021;13:689098. [CrossRef]
- Liu E, Sun L, Zhang Y, Wang A, Yan J. Aquaporin4 Knockout Aggravates Early Brain Injury Following Subarachnoid Hemorrhage Through Impairment of the Glymphatic System in Rat Brain. Acta Neurochir Suppl. 2020;127:59-64. [CrossRef]
- Tang Y, Wu P, Su J, Xiang J, Cai D, Dong Q. Effects of Aquaporin-4 on edema formation following intracerebral hemorrhage. Exp Neurol. 2010;223(2):485-95. [CrossRef]
- Shi WZ, Zhao CZ, Zhao B, Shi QJ, Zhang LH, Wang YF, et al. Aggravated inflammation and increased expression of cysteinyl leukotriene receptors in the brain after focal cerebral ischemia in AQP4-deficient mice. Neurosci Bull. 2012;28(6):680-92. [CrossRef]
- Sun C, Lin L, Yin L, Hao X, Tian J, Zhang X, et al. Acutely Inhibiting AQP4 With TGN-020 Improves Functional Outcome by Attenuating Edema and Peri-Infarct Astrogliosis After Cerebral Ischemia. Front Immunol. 2022;13:870029. [CrossRef]
- Patabendige A, Chen R. Astrocytic aquaporin 4 subcellular translocation as a therapeutic target for cytotoxic edema in ischemic stroke. Neural Regen Res. 2022;17(12):2666-8. [CrossRef]
- Pirici I, Balsanu TA, Bogdan C, Margaritescu C, Divan T, Vitalie V, et al. Inhibition of Aquaporin-4 Improves the Outcome of Ischaemic Stroke and Modulates Brain Paravascular Drainage Pathways. Int J Mol Sci. 2017;19(1). [CrossRef]
- Pu T, Zou W, Feng W, Zhang Y, Wang L, Wang H, et al. Persistent Malfunction of Glymphatic and Meningeal Lymphatic Drainage in a Mouse Model of Subarachnoid Hemorrhage. Exp Neurobiol. 2019;28(1):104-18. [CrossRef]
- Golanov EV, Bovshik EI, Wong KK, Pautler RG, Foster CH, Federley RG, et al. Subarachnoid hemorrhage - Induced block of cerebrospinal fluid flow: Role of brain coagulation factor III (tissue factor). J Cereb Blood Flow Metab. 2018;38(5):793-808. [CrossRef]
- Gaberel T, Gakuba C, Goulay R, Martinez De Lizarrondo S, Hanouz JL, Emery E, et al. Impaired glymphatic perfusion after strokes revealed by contrast-enhanced MRI: a new target for fibrinolysis? Stroke. 2014;45(10):3092-6. [CrossRef]
- Goulay R, Flament J, Gauberti M, Naveau M, Pasquet N, Gakuba C, et al. Subarachnoid Hemorrhage Severely Impairs Brain Parenchymal Cerebrospinal Fluid Circulation in Nonhuman Primate. Stroke. 2017;48(8):2301-5. [CrossRef]
- Lin L, Hao X, Li C, Sun C, Wang X, Yin L, et al. Impaired glymphatic system in secondary degeneration areas after ischemic stroke in rats. J Stroke Cerebrovasc Dis. 2020;29(7):104828. [CrossRef]
- Back DB, Choi BR, Han JS, Kwon KJ, Choi DH, Shin CY, et al. Characterization of Tauopathy in a Rat Model of Post-Stroke Dementia Combining Acute Infarct and Chronic Cerebral Hypoperfusion. Int J Mol Sci. 2020;21(18). [CrossRef]
- Zhang C, Sha J, Cai L, Xia Y, Li D, Zhao H, et al. Evaluation of the Glymphatic System Using the DTI-ALPS Index in Patients with Spontaneous Intracerebral Haemorrhage. Oxid Med Cell Longev. 2022;2022:2694316. [CrossRef]
- Zhang S, Yu W, Zhang X, Cheng H, Zhang Z, Gao S, et al. Glymphatic dysfunction as a biomarker for post-stroke cognitive impairment. Sci Rep. 2025;15(1):19382. [CrossRef]
- Qin Y, Li X, Qiao Y, Zou H, Qian Y, Li X, et al. DTI-ALPS: An MR biomarker for motor dysfunction in patients with subacute ischemic stroke. Front Neurosci. 2023;17:1132393. [CrossRef]
- Wang Y, Yang M, Zeng X, Wang S, Zhang W, Wang W, et al. Glymphatic dysfunction assessed by DTI-ALPS index predicts early cognitive impairment in acute subcortical infarcts: a prospective clinical cohort study. Front Neurol. 2025;16:1605889. [CrossRef]
- Chen Q, Zhong T, Liu J, Yuan B, Gao H. Chronic Glymphatic Dysfunction Modulates Domain-Specific Cognitive Recovery After Stroke: A DTI-ALPS Lesion Stratification Study. CNS Neurosci Ther. 2025;31(7):e70512. [CrossRef]
- Yang J, Liu Y, Ma Y, Zhang W, Han L, Feng H, et al. Association of glymphatic clearance function with imaging markers and risk factors of cerebral small vessel disease. J Stroke Cerebrovasc Dis. 2025;34(2):108187. [CrossRef]
- Toh CH, Siow TY. Glymphatic Dysfunction in Patients With Ischemic Stroke. Front Aging Neurosci. 2021;13:756249. [CrossRef]
- Chojdak-Lukasiewicz J, Dziadkowiak E, Zimny A, Paradowski B. Cerebral small vessel disease: A review. Adv Clin Exp Med. 2021;30(3):349-56. [CrossRef]
- Zhang W, Zhou Y, Wang J, Gong X, Chen Z, Zhang X, et al. Glymphatic clearance function in patients with cerebral small vessel disease. Neuroimage. 2021;238:118257. [CrossRef]
- Zhang X, Pei X, Shi Y, Yang Y, Bai X, Chen T, et al. Unveiling connections between venous disruption and cerebral small vessel disease using diffusion tensor image analysis along perivascular space (DTI-ALPS): A 7-T MRI study. Int J Stroke. 2025;20(4):497-506. [CrossRef]
- Hong H, Tozer DJ, Markus HS. Relationship of Perivascular Space Markers With Incident Dementia in Cerebral Small Vessel Disease. Stroke. 2024;55(4):1032-40. [CrossRef]
- Diamandi J, Hone A, Alizadeh M, Tjoumakaris S, Gooch R, Jabbour P, et al. Evaluation of DTI-ALPS index in patients with acute ischemic stroke. Journal of NeuroInterventional Surgery. 2025;17:A47-A8.
- Michalaki E, Pulliam AN, Datta Roy PM, Dixon JB, LaPlaca MC. Near-Infrared Imaging of Glymphatic Clearance in a Pre-Clinical Model of Repetitive Closed Head Traumatic Brain Injury. Neurotrauma Rep. 2025;6(1):115-28. [CrossRef]
- Li L, Chopp M, Ding G, Davoodi-Bojd E, Zhang L, Li Q, et al. MRI detection of impairment of glymphatic function in rat after mild traumatic brain injury. Brain Res. 2020;1747:147062. [CrossRef]
- Christensen J, Wright DK, Yamakawa GR, Shultz SR, Mychasiuk R. Repetitive Mild Traumatic Brain Injury Alters Glymphatic Clearance Rates in Limbic Structures of Adolescent Female Rats. Sci Rep. 2020;10(1):6254. [CrossRef]
- Hussain R, Tithof J, Wang W, Cheetham-West A, Song W, Peng W, et al. Potentiating glymphatic drainage minimizes post-traumatic cerebral oedema. Nature. 2023;623(7989):992-1000. [CrossRef]
- Dadgostar E, Rahimi S, Nikmanzar S, Nazemi S, Naderi Taheri M, Alibolandi Z, et al. Aquaporin 4 in Traumatic Brain Injury: From Molecular Pathways to Therapeutic Target. Neurochem Res. 2022;47(4):860-71. [CrossRef]
- Braun M, Sevao M, Keil SA, Gino E, Wang MX, Lee J, et al. Macroscopic changes in aquaporin-4 underlie blast traumatic brain injury-related impairment in glymphatic function. Brain. 2024;147(6):2214-29. [CrossRef]
- Xiong A, Xiong R, Yu J, Liu Y, Liu K, Jin G, et al. Aquaporin-4 is a potential drug target for traumatic brain injury via aggravating the severity of brain edema. Burns Trauma. 2021;9:tkaa050. [CrossRef]
- Ren Z, Iliff JJ, Yang L, Yang J, Chen X, Chen MJ, et al. 'Hit & Run' model of closed-skull traumatic brain injury (TBI) reveals complex patterns of post-traumatic AQP4 dysregulation. J Cereb Blood Flow Metab. 2013;33(6):834-45. [CrossRef]
- Iliff JJ, Chen MJ, Plog BA, Zeppenfeld DM, Soltero M, Yang L, et al. Impairment of glymphatic pathway function promotes tau pathology after traumatic brain injury. J Neurosci. 2014;34(49):16180-93. [CrossRef]
- Guan Y, Li L, Chen J, Lu H. Effect of AQP4-RNAi in treating traumatic brain edema: Multi-modal MRI and histopathological changes of early stage edema in a rat model. Exp Ther Med. 2020;19(3):2029-36. [CrossRef]
- Yang DX, Sun Z, Yu MM, Zou QQ, Li PY, Zhang JK, et al. Associations of MRI-Derived Glymphatic System Impairment With Global White Matter Damage and Cognitive Impairment in Mild Traumatic Brain Injury: A DTI-ALPS Study. J Magn Reson Imaging. 2024;59(2):639-47. [CrossRef]
- Wang X, Deng L, Liu X, Cheng S, Zhan Y, Chen J. Relationship between glymphatic system dysfunction and cognitive impairment in patients with mild-to-moderate chronic traumatic brain injury: an analysis of the analysis along the perivascular space (ALPS) index. Quant Imaging Med Surg. 2024;14(12):9246-57. [CrossRef]
- Park JH, Bae YJ, Kim JS, Jung WS, Choi JW, Roh TH, et al. Glymphatic system evaluation using diffusion tensor imaging in patients with traumatic brain injury. Neuroradiology. 2023;65(3):551-7. [CrossRef]
- Butler T, Zhou L, Ozsahin I, Wang XH, Garetti J, Zetterberg H, et al. Glymphatic clearance estimated using diffusion tensor imaging along perivascular spaces is reduced after traumatic brain injury and correlates with plasma neurofilament light, a biomarker of injury severity. Brain Commun. 2023;5(3):fcad134. [CrossRef]
- Dai Z, Yang Z, Li Z, Li M, Sun H, Zhuang Z, et al. Increased glymphatic system activity in patients with mild traumatic brain injury. Front Neurol. 2023;14:1148878. [CrossRef]
- Zhang E, Wan X, Yang L, Wang D, Chen Z, Chen Y, et al. Omega-3 Polyunsaturated Fatty Acids Alleviate Traumatic Brain Injury by Regulating the Glymphatic Pathway in Mice. Front Neurol. 2020;11:707. [CrossRef]
- Lv C, Han S, Sha Z, Liu M, Dong S, Zhang C, et al. Cerebral glucagon-like peptide-1 receptor activation alleviates traumatic brain injury by glymphatic system regulation in mice. CNS Neurosci Ther. 2023;29(12):3876-88. [CrossRef]
- Dai J, Lin W, Zheng M, Liu Q, He B, Luo C, et al. Alterations in AQP4 expression and polarization in the course of motor neuron degeneration in SOD1G93A mice. Mol Med Rep. 2017;16(2):1739-46. [CrossRef]
- Watanabe-Matsumoto S, Moriwaki Y, Okuda T, Ohara S, Yamanaka K, Abe Y, et al. Dissociation of blood-brain barrier disruption and disease manifestation in an aquaporin-4-deficient mouse model of amyotrophic lateral sclerosis. Neurosci Res. 2018;133:48-57. [CrossRef]
- Ng Kee Kwong KC, Mehta AR, Nedergaard M, Chandran S. Defining novel functions for cerebrospinal fluid in ALS pathophysiology. Acta Neuropathol Commun. 2020;8(1):140. [CrossRef]
- Zamani A, Walker AK, Rollo B, Ayers KL, Farah R, O'Brien TJ, et al. Impaired glymphatic function in the early stages of disease in a TDP-43 mouse model of amyotrophic lateral sclerosis. Transl Neurodegener. 2022;11(1):17. [CrossRef]
- Huang NX, Zeng JY, Huang HW, Fang SY, Chen S, Li JQ, et al. Association of glymphatic system disturbance with neural dysfunction in amyotrophic lateral sclerosis. Quant Imaging Med Surg. 2025;15(4):3445-57. [CrossRef]
- Choi Y, Jung HJ, Jung HK, Jeong E, Kim S, Kim JY, et al. In vivo imaging markers of glymphatic dysfunction in amyotrophic lateral sclerosis: Analysis of ALPS index and choroid plexus volume. J Neurol Sci. 2025;469:123393. [CrossRef]
- Baek SH, Tae WS, Park JW, Kim BJ. Assessment of the glymphatic dysfunction in amyotrophic lateral sclerosis using the diffusion tensor imaging along the perivascular spaces index: a pilot study. Front Aging Neurosci. 2025;17:1570327. [CrossRef]
- Liu S, Sun X, Ren Q, Chen Y, Dai T, Yang Y, et al. Glymphatic dysfunction in patients with early-stage amyotrophic lateral sclerosis. Brain. 2024;147(1):100-8. [CrossRef]
- Sharkey RJ, Cortese F, Goodyear BG, Korngut LW, Jacob SM, Sharkey KA, et al. Longitudinal analysis of glymphatic function in amyotrophic lateral sclerosis and primary lateral sclerosis. Brain. 2024;147(12):4026-32. [CrossRef]
- Owasil R, O'Neill R, Keable A, Nimmo J, MacGregor Sharp M, Kelly L, et al. The Pattern of AQP4 Expression in the Ageing Human Brain and in Cerebral Amyloid Angiopathy. Int J Mol Sci. 2020;21(4). [CrossRef]
- Gupta RK, Kanungo M. Glial molecular alterations with mouse brain development and aging: up-regulation of the Kir4.1 and aquaporin-4. Age (Dordr). 2013;35(1):59-67. [CrossRef]
- Lynch KM, Sepehrband F, Toga AW, Choupan J. Brain perivascular space imaging across the human lifespan. Neuroimage. 2023;271:120009. [CrossRef]
- Bailes SM, Williams SD, Ashenagar B, Licata J, Bosli MY, Dormes BJ, et al. The aging human brain exhibits reduced cerebrospinal fluid flow during sleep due to both neural and vascular factors. bioRxiv. 2025. [CrossRef]
- Zhou Y, Cai J, Zhang W, Gong X, Yan S, Zhang K, et al. Impairment of the Glymphatic Pathway and Putative Meningeal Lymphatic Vessels in the Aging Human. Ann Neurol. 2020;87(3):357-69. [CrossRef]
- Jin R, Chan AKY, Wu J, Lee TMC. Relationships between Inflammation and Age-Related Neurocognitive Changes. Int J Mol Sci. 2022;23(20). [CrossRef]
- Da Mesquita S, Herz J, Wall M, Dykstra T, de Lima KA, Norris GT, et al. Aging-associated deficit in CCR7 is linked to worsened glymphatic function, cognition, neuroinflammation, and beta-amyloid pathology. Sci Adv. 2021;7(21). [CrossRef]
- Che Mohd Nassir CMN, Che Ramli MD, Mohamad Ghazali M, Jaffer U, Abdul Hamid H, Mehat MZ, et al. The Microbiota-Gut-Brain Axis: Key Mechanisms Driving Glymphopathy and Cerebral Small Vessel Disease. Life (Basel). 2024;15(1). [CrossRef]
- Kim S, Kwon SH, Kam TI, Panicker N, Karuppagounder SS, Lee S, et al. Transneuronal Propagation of Pathologic alpha-Synuclein from the Gut to the Brain Models Parkinson's Disease. Neuron. 2019;103(4):627-41 e7. [CrossRef]
- Zhao YF, Wei DN, Tang Y. Gut Microbiota Regulate Astrocytic Functions in the Brain: Possible Therapeutic Consequences. Curr Neuropharmacol. 2021;19(8):1354-66. [CrossRef]
- Shannon KM. Gut-Derived Sterile Inflammation and Parkinson's Disease. Front Neurol. 2022;13:831090. [CrossRef]
- Verheggen ICM, Van Boxtel MPJ, Verhey FRJ, Jansen JFA, Backes WH. Interaction between blood-brain barrier and glymphatic system in solute clearance. Neurosci Biobehav Rev. 2018;90:26-33. [CrossRef]
- Anand N, Gorantla VR, Chidambaram SB. The Role of Gut Dysbiosis in the Pathophysiology of Neuropsychiatric Disorders. Cells. 2022;12(1). [CrossRef]
- Salminen A. Aryl hydrocarbon receptor impairs circadian regulation in Alzheimer's disease: Potential impact on glymphatic system dysfunction. Eur J Neurosci. 2024;60(2):3901-20. [CrossRef]
- Chi L, Cheng X, Lin L, Yang T, Sun J, Feng Y, et al. Porphyromonas gingivalis-Induced Cognitive Impairment Is Associated With Gut Dysbiosis, Neuroinflammation, and Glymphatic Dysfunction. Front Cell Infect Microbiol. 2021;11:755925. [CrossRef]
- He XF, Li LL, Xian WB, Li MY, Zhang LY, Xu JH, et al. Chronic colitis exacerbates NLRP3-dependent neuroinflammation and cognitive impairment in middle-aged brain. J Neuroinflammation. 2021;18(1):153. [CrossRef]
- Xie L, Kang H, Xu Q, Chen MJ, Liao Y, Thiyagarajan M, et al. Sleep drives metabolite clearance from the adult brain. Science. 2013;342(6156):373-7. [CrossRef]
- Achariyar TM, Li B, Peng W, Verghese PB, Shi Y, McConnell E, et al. Glymphatic distribution of CSF-derived apoE into brain is isoform specific and suppressed during sleep deprivation. Mol Neurodegener. 2016;11(1):74. [CrossRef]
- Demiral SB, Tomasi D, Sarlls J, Lee H, Wiers CE, Zehra A, et al. Apparent diffusion coefficient changes in human brain during sleep - Does it inform on the existence of a glymphatic system? Neuroimage. 2019;185:263-73. [CrossRef]
- Vasciaveo V, Iadarola A, Casile A, Dante D, Morello G, Minotta L, et al. Sleep fragmentation affects glymphatic system through the different expression of AQP4 in wild type and 5xFAD mouse models. Acta Neuropathol Commun. 2023;11(1):16. [CrossRef]
- Saito Y, Hayakawa Y, Kamagata K, Kikuta J, Mita T, Andica C, et al. Glymphatic system impairment in sleep disruption: diffusion tensor image analysis along the perivascular space (DTI-ALPS). Jpn J Radiol. 2023;41(12):1335-43. [CrossRef]
- Lee HJ, Lee DA, Shin KJ, Park KM. Glymphatic system dysfunction in obstructive sleep apnea evidenced by DTI-ALPS. Sleep Med. 2022;89:176-81. [CrossRef]
- Eide PK, Pripp AH, Berge B, Hrubos-Strom H, Ringstad G, Valnes LM. Altered glymphatic enhancement of cerebrospinal fluid tracer in individuals with chronic poor sleep quality. J Cereb Blood Flow Metab. 2022;42(9):1676-92. [CrossRef]
- Ye M, Kang X, Karlsson IK, Wang Y, Ji Q, Liu Q, et al. Associations between Sleep Disorders and Impulsive-Compulsive Behaviors in Parkinson's Disease: A Prospective Cohort Study. Neuroepidemiology. 2024;58(4):256-63. [CrossRef]
- Yoon SH, Kim HK, Lee JH, Chun JH, Sohn YH, Lee PH, et al. Association of Sleep Disturbances With Brain Amyloid and Tau Burden, Cortical Atrophy, and Cognitive Dysfunction Across the AD Continuum. Neurology. 2023;101(21):e2162-e71. [CrossRef]
- Hauglund NL, Andersen M, Tokarska K, Radovanovic T, Kjaerby C, Sorensen FL, et al. Norepinephrine-mediated slow vasomotion drives glymphatic clearance during sleep. Cell. 2025;188(3):606-22 e17. [CrossRef]
- Hablitz LM, Vinitsky HS, Sun Q, Staeger FF, Sigurdsson B, Mortensen KN, et al. Increased glymphatic influx is correlated with high EEG delta power and low heart rate in mice under anesthesia. Sci Adv. 2019;5(2):eaav5447. [CrossRef]
- Liu G, Mestre H, Sweeney AM, Sun Q, Weikop P, Du T, et al. Direct Measurement of Cerebrospinal Fluid Production in Mice. Cell Rep. 2020;33(12):108524. [CrossRef]
- Ozturk BO, Monte B, Koundal S, Dai F, Benveniste H, Lee H. Disparate volumetric fluid shifts across cerebral tissue compartments with two different anesthetics. Fluids Barriers CNS. 2021;18(1):1. [CrossRef]
- Dong R, Han Y, Lv P, Jiang L, Wang Z, Peng L, et al. Long-term isoflurane anesthesia induces cognitive deficits via AQP4 depolarization mediated blunted glymphatic inflammatory proteins clearance. J Cereb Blood Flow Metab. 2024;44(8):1450-66. [CrossRef]
- Benveniste H, Lee H, Ding F, Sun Q, Al-Bizri E, Makaryus R, et al. Anesthesia with Dexmedetomidine and Low-dose Isoflurane Increases Solute Transport via the Glymphatic Pathway in Rat Brain When Compared with High-dose Isoflurane. Anesthesiology. 2017;127(6):976-88. [CrossRef]
- Sagirov AF, Sergeev TV, Shabrov AV, Yurov AY, Guseva NL, Agapova EA. Postural influence on intracranial fluid dynamics: an overview. J Physiol Anthropol. 2023;42(1):5. [CrossRef]
- Strbacko I, Rados M, Jurjevic I, Oreskovic D, Klarica M. Body position influence on cerebrospinal fluid volume redistribution inside the cranial and spinal CSF compartments. Front Hum Neurosci. 2024;18:1463740. [CrossRef]
- Bothwell SW, Janigro D, Patabendige A. Cerebrospinal fluid dynamics and intracranial pressure elevation in neurological diseases. Fluids Barriers CNS. 2019;16(1):9. [CrossRef]
- Ren X, Liu S, Lian C, Li H, Li K, Li L, et al. Dysfunction of the Glymphatic System as a Potential Mechanism of Perioperative Neurocognitive Disorders. Front Aging Neurosci. 2021;13:659457. [CrossRef]
- Lee H, Xie L, Yu M, Kang H, Feng T, Deane R, et al. The Effect of Body Posture on Brain Glymphatic Transport. J Neurosci. 2015;35(31):11034-44. [CrossRef]
- Muccio M, Chu D, Minkoff L, Kulkarni N, Damadian B, Damadian RV, et al. Upright versus supine MRI: effects of body position on craniocervical CSF flow. Fluids Barriers CNS. 2021;18(1):61. [CrossRef]
- Alperin N, Lee SH, Sivaramakrishnan A, Hushek SG. Quantifying the effect of posture on intracranial physiology in humans by MRI flow studies. J Magn Reson Imaging. 2005;22(5):591-6. [CrossRef]
- Lundgaard I, Wang W, Eberhardt A, Vinitsky HS, Reeves BC, Peng S, et al. Beneficial effects of low alcohol exposure, but adverse effects of high alcohol intake on glymphatic function. Sci Rep. 2018;8(1):2246. [CrossRef]
- Liu Q, Yan L, Huang M, Zeng H, Satyanarayanan SK, Shi Z, et al. Experimental alcoholism primes structural and functional impairment of the glymphatic pathway. Brain Behav Immun. 2020;85:106-19. [CrossRef]
- Tsugawa S, Ueno F, Sakuma M, Tani H, Ochi R, Graff-Guerrero A, et al. Effects of short-term exposure to moderate amounts of alcohol on brain volume. Neuropsychopharmacol Rep. 2025;45(1):e12500. [CrossRef]
- Cheng Y, Liu X, Ma X, Garcia R, Belfield K, Haorah J. Alcohol promotes waste clearance in the CNS via brain vascular reactivity. Free Radic Biol Med. 2019;143:115-26. [CrossRef]
- Kumar M, Swanson N, Ray S, Buch S, Saraswathi V, Sil S. Astrocytes in Amyloid Generation and Alcohol Metabolism: Implications of Alcohol Use in Neurological Disorder(s). Cells. 2024;13(14). [CrossRef]
- Hasegawa H, Kondo M. Astrocytic Responses to Binge Alcohol Intake in the Mouse Hindbrain. Biol Pharm Bull. 2023;46(9):1194-202. [CrossRef]
- Guizzetti M, Mangieri RA, Ezerskiy LA, Hashimoto JG, Bajo M, Farris SP, et al. Astrocytes and Alcohol Throughout the Lifespan. Biol Psychiatry. 2025. [CrossRef]
- Nedergaard M, Goldman SA. Glymphatic failure as a final common pathway to dementia. Science. 2020;370(6512):50-6. [CrossRef]
- Kaur J, Fahmy LM, Davoodi-Bojd E, Zhang L, Ding G, Hu J, et al. Waste Clearance in the Brain. Front Neuroanat. 2021;15:665803. [CrossRef]
- Carlstrom LP, Eltanahy A, Perry A, Rabinstein AA, Elder BD, Morris JM, et al. A clinical primer for the glymphatic system. Brain. 2022;145(3):843-57. [CrossRef]
- Eidsvaag VA, Enger R, Hansson HA, Eide PK, Nagelhus EA. Human and mouse cortical astrocytes differ in aquaporin-4 polarization toward microvessels. Glia. 2017;65(6):964-73. [CrossRef]
- Taoka T, Naganawa S. Glymphatic imaging using MRI. J Magn Reson Imaging. 2020;51(1):11-24. [CrossRef]
- Mestre H, Mori Y, Nedergaard M. The Brain's Glymphatic System: Current Controversies. Trends Neurosci. 2020;43(7):458-66. [CrossRef]
- Smith AJ, Yao X, Dix JA, Jin BJ, Verkman AS. Test of the 'glymphatic' hypothesis demonstrates diffusive and aquaporin-4-independent solute transport in rodent brain parenchyma. Elife. 2017;6. [CrossRef]
- Mestre H, Hablitz LM, Xavier AL, Feng W, Zou W, Pu T, et al. Aquaporin-4-dependent glymphatic solute transport in the rodent brain. Elife. 2018;7. [CrossRef]
Figure 1.
Glymphatic system physiology and dysfunction as a convergent mechanism across CNS disorders. Cross-sectional schematic of cerebral parenchyma, comparing healthy (upper row) and dysfunctional (lower row) glymphatic system function. The glymphatic system is a brain-wide perivascular network that facilitates cerebrospinal fluid-interstitial fluid exchange and clearance of metabolic waste. CSF enters (A) the brain along periarterial spaces (2) of penetrating arterioles (1), driven by arterial pulsatility and pressure gradients, and crosses into the interstitium through aquaporin-4 (AQP4) water channels (3) expressed on the end feet of astrocytes (4). The end feet ensheathe the cerebral vasculature and form the outer boundary of the perivascular spaces, with proper polarization (B) of AQP4 channels at the end feet being crucial for glymphatic function. A convective CSF and ISF bulk flow (C) arises through the brain parenchyma, populated by neurons (5) and surveillant ramified microglia (6). The mixed CSF-ISF then exits (D) the brain along perivenous spaces (7) of venules (8), draining toward the venous sinuses (9) and dural lymphatic vessels (10) ultimately towards the cervical lymph nodes (not depicted). Glymphatic function contributes to the clearance of neurotoxic byproducts, including amyloid-β (Aβ), tau, and α-synuclein. In the dysfunctional state (lower row), loss of perivascular localization of AQP4 (depolarization, E) impairs CSF-ISF exchange and waste clearance, while the perivascular spaces become enlarged (F). Microglia cells transition from ramified to amoeboid morphology indicating activation (G). Decreased glymphatic flow (H) may result in accumulation of Aβ plaques (I), tau neurofibrillary tangles (J), α-synuclein aggregates (K), and pro-inflammatory cytokines (L), contributing to neuroinflammation and neuronal dysfunction. Some illustrations were adapted from Servier Medical Art (smart.servier.com), licensed under CC BY 4.0.
Figure 1.
Glymphatic system physiology and dysfunction as a convergent mechanism across CNS disorders. Cross-sectional schematic of cerebral parenchyma, comparing healthy (upper row) and dysfunctional (lower row) glymphatic system function. The glymphatic system is a brain-wide perivascular network that facilitates cerebrospinal fluid-interstitial fluid exchange and clearance of metabolic waste. CSF enters (A) the brain along periarterial spaces (2) of penetrating arterioles (1), driven by arterial pulsatility and pressure gradients, and crosses into the interstitium through aquaporin-4 (AQP4) water channels (3) expressed on the end feet of astrocytes (4). The end feet ensheathe the cerebral vasculature and form the outer boundary of the perivascular spaces, with proper polarization (B) of AQP4 channels at the end feet being crucial for glymphatic function. A convective CSF and ISF bulk flow (C) arises through the brain parenchyma, populated by neurons (5) and surveillant ramified microglia (6). The mixed CSF-ISF then exits (D) the brain along perivenous spaces (7) of venules (8), draining toward the venous sinuses (9) and dural lymphatic vessels (10) ultimately towards the cervical lymph nodes (not depicted). Glymphatic function contributes to the clearance of neurotoxic byproducts, including amyloid-β (Aβ), tau, and α-synuclein. In the dysfunctional state (lower row), loss of perivascular localization of AQP4 (depolarization, E) impairs CSF-ISF exchange and waste clearance, while the perivascular spaces become enlarged (F). Microglia cells transition from ramified to amoeboid morphology indicating activation (G). Decreased glymphatic flow (H) may result in accumulation of Aβ plaques (I), tau neurofibrillary tangles (J), α-synuclein aggregates (K), and pro-inflammatory cytokines (L), contributing to neuroinflammation and neuronal dysfunction. Some illustrations were adapted from Servier Medical Art (smart.servier.com), licensed under CC BY 4.0.
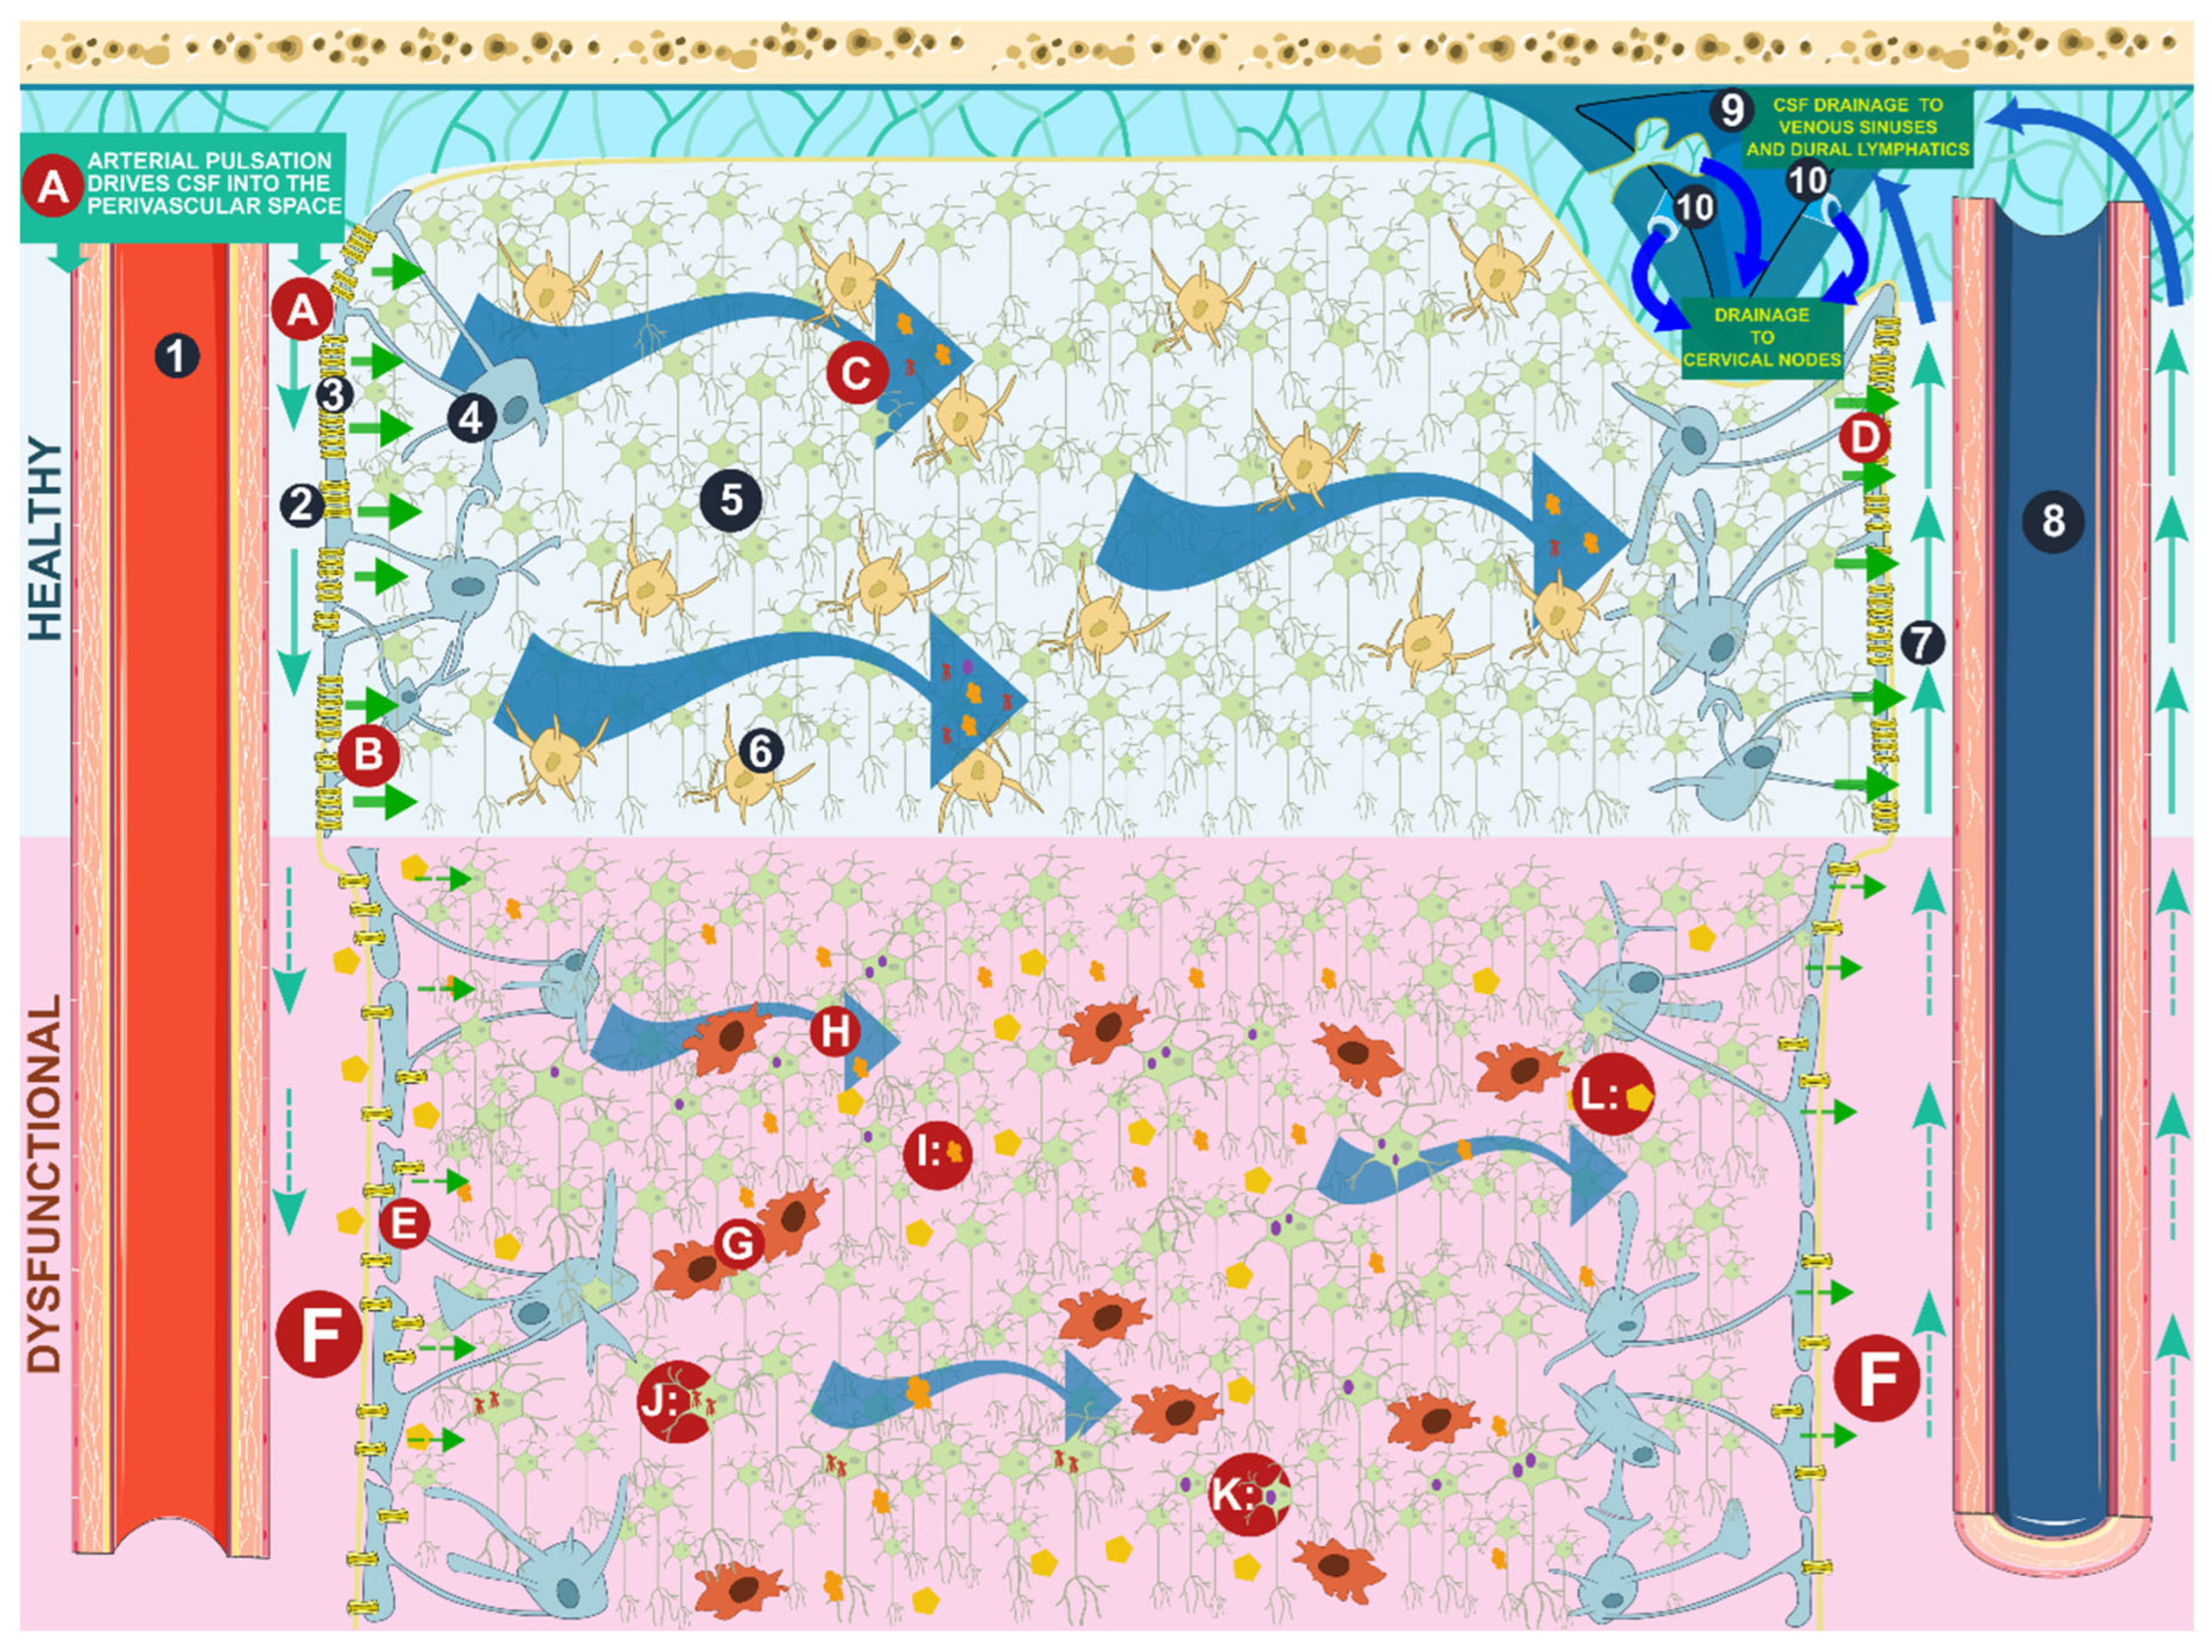
Figure 2.
Convergent modulators of glymphatic clearance and associated CNS conditions. The glymphatic system (central hub) is a brain-wide perivascular network that facilitates cerebrospinal fluid–interstitial fluid exchange and clearance of metabolic waste and is modulated by three converging systems: Inflammaging could impair glymphatic clearance through chronic low-grade immune activation, with mechanisms including loss of aquaporin-4 perivascular polarization, vascular stiffening with reduced arterial pulsatility, and accumulation of immune cells in perivascular spaces. The gut-brain axis may contribute via gut dysbiosis-driven peripheral inflammation and pro-inflammatory cytokine release, vagal signaling, and short-chain fatty acid–mediated disruption of blood–brain barrier integrity. Lifestyle modulators can exert multivalent, context- and dose-dependent effects: adequate sleep, supine/lateral body posture, low-dose alcohol, and slow-wave-promoting anesthesia enhance glymphatic transport, while sleep disruption, upright posture, chronic high-dose alcohol exposure, and prolonged high-dose isoflurane impair it. Warm-colored arrows indicate impairing influences on glymphatic function; the paired cool and warm arrows from the lifestyle zone reflect the twoway nature of those modulators; the grey associative arrow links glymphatic dysfunction to the listed conditions without implying direct causality. AQP4, aquaporin-4; BBB, blood–brain barrier; CNS, central nervous system; CSF, cerebrospinal fluid; ICH, intracerebral haemorrhage; iNPH, idiopathic normal pressure hydrocephalus. Some illustrations were adapted from Servier Medical Art (smart.servier.com), licensed under CC BY 4.0.
Figure 2.
Convergent modulators of glymphatic clearance and associated CNS conditions. The glymphatic system (central hub) is a brain-wide perivascular network that facilitates cerebrospinal fluid–interstitial fluid exchange and clearance of metabolic waste and is modulated by three converging systems: Inflammaging could impair glymphatic clearance through chronic low-grade immune activation, with mechanisms including loss of aquaporin-4 perivascular polarization, vascular stiffening with reduced arterial pulsatility, and accumulation of immune cells in perivascular spaces. The gut-brain axis may contribute via gut dysbiosis-driven peripheral inflammation and pro-inflammatory cytokine release, vagal signaling, and short-chain fatty acid–mediated disruption of blood–brain barrier integrity. Lifestyle modulators can exert multivalent, context- and dose-dependent effects: adequate sleep, supine/lateral body posture, low-dose alcohol, and slow-wave-promoting anesthesia enhance glymphatic transport, while sleep disruption, upright posture, chronic high-dose alcohol exposure, and prolonged high-dose isoflurane impair it. Warm-colored arrows indicate impairing influences on glymphatic function; the paired cool and warm arrows from the lifestyle zone reflect the twoway nature of those modulators; the grey associative arrow links glymphatic dysfunction to the listed conditions without implying direct causality. AQP4, aquaporin-4; BBB, blood–brain barrier; CNS, central nervous system; CSF, cerebrospinal fluid; ICH, intracerebral haemorrhage; iNPH, idiopathic normal pressure hydrocephalus. Some illustrations were adapted from Servier Medical Art (smart.servier.com), licensed under CC BY 4.0.
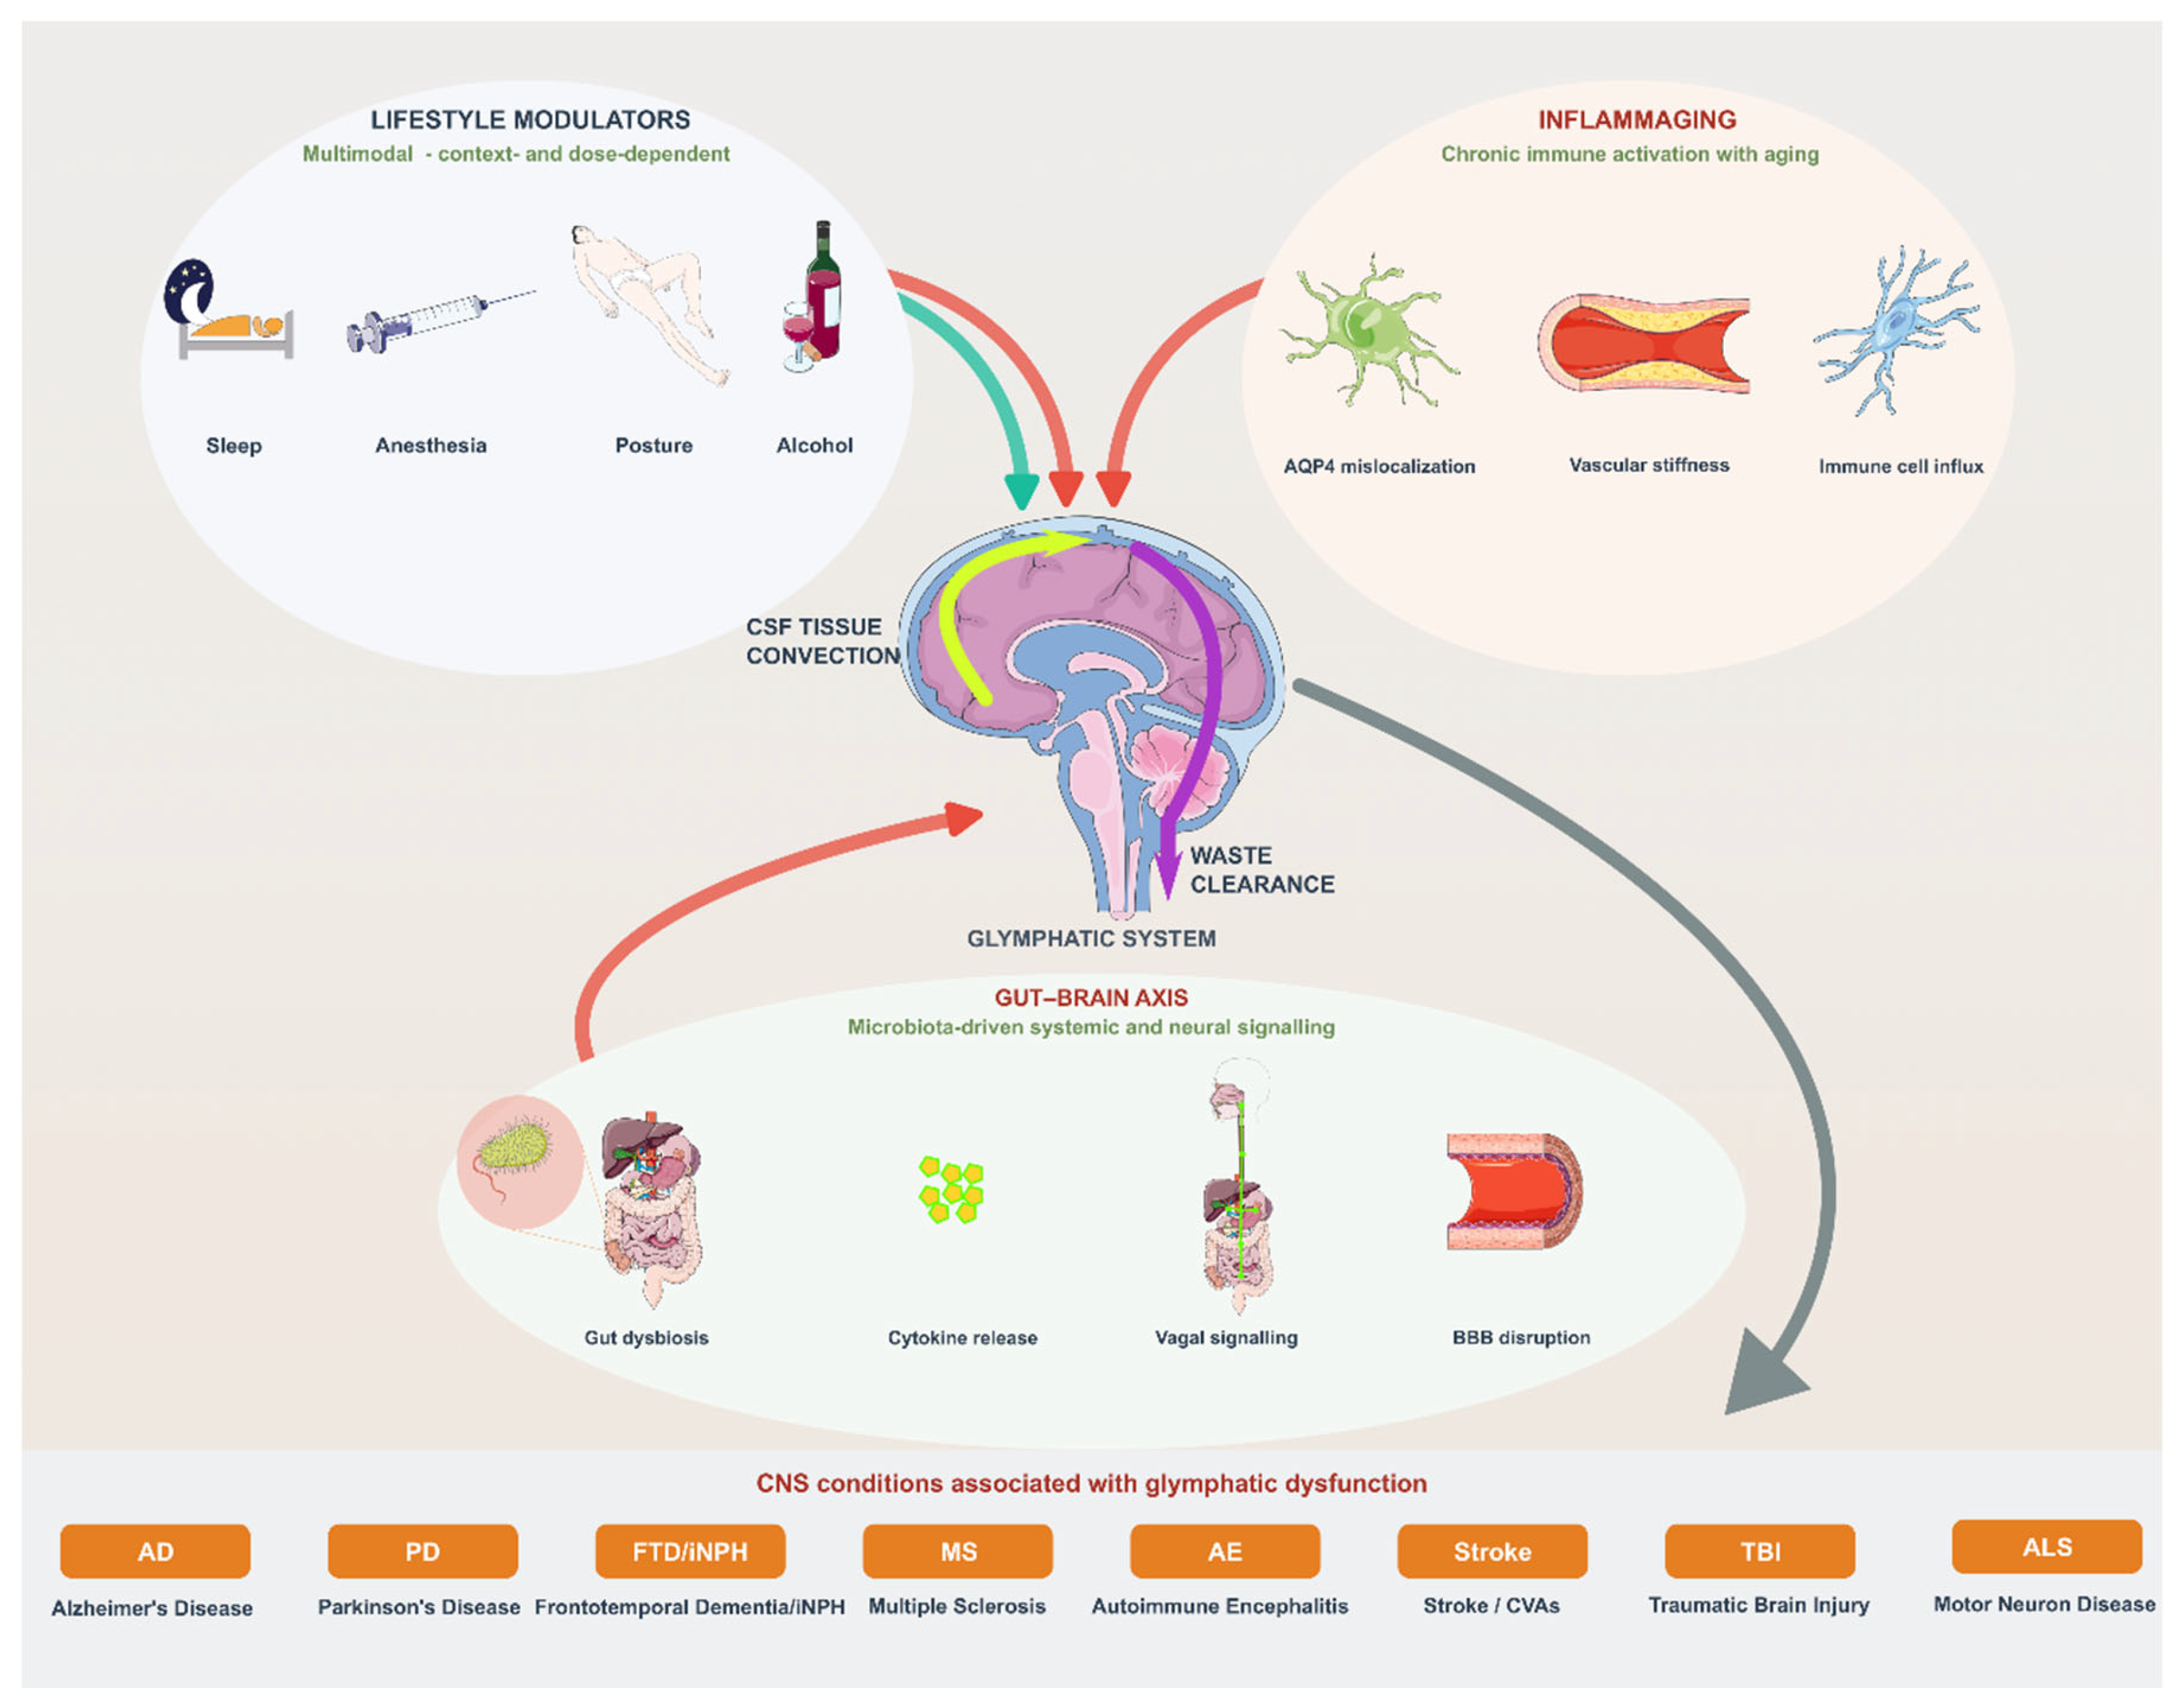
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.