

Submitted:
01 October 2026
Posted:
02 October 2026
You are already at the latest version
Abstract
Background/Objectives: Postoperative management after cataract surgery involves topical anti-inflammatory and antimicrobial treatments, whose clinical performance may be affected by adherence, administration technique, and intraocular exposure. This study evaluated a biodegradable poly(lactic-co-glycolic acid) intracameral implant containing moxifloxacin hydrochloride and dexamethasone, designed for intraoperative placement. Methods: Clinical tolerability, anti-inflammatory activity in a uveitis model, and antibacterial performance following a low-inoculum intravitreal challenge with Pseudomonas aeruginosa were evaluated in New Zealand White rabbits. Aqueous humor pharmacokinetic profiles were also assessed in phakic and aphakic eyes. Clinical follow-up included slit-lamp biomicroscopy and intraocular pressure measurements. Concentration–time data were analyzed by means of nonlinear mixed-effects models and model-based simulations. Results: No visible implant material remained four weeks after insertion. A transient pseudo-membrane was observed shortly after implantation in some implanted eyes, but it resolved spontaneously and was not accompanied by clinical inflammatory signs. No sustained increase in intraocular pressure was observed during follow-up. Untreated bacterially challenged eyes rapidly developed severe endophthalmitis, whereas implant-treated eyes showed no clinical evidence of endophthalmitis. In the exploratory uveitis experiment, implant-treated eyes showed lower clinical inflammatory scores and faster recovery than matched eyes without the implant. Model-based simulations suggested persistent dexamethasone exposure through day 30, whereas moxifloxacin reached an early peak and was predominantly below the limit of quantification from day 7 onward. Conclusions: These findings provide preliminary preclinical proof-of-concept evidence supporting the clinical tolerability and pharmacological activity of the implant under the experimental conditions evaluated. The results are hypothesis-generating, should not be extrapolated to clinical safety or efficacy, and do not demonstrate microbiological eradication. Further studies with larger cohorts, pseudophakic models, microbiological and histopathological endpoints, and optimized pharmacokinetic sampling are required.
Keywords:
biodegradable implant
; cataract surgery
; endophthalmitis
; pharmacokinetics
1. Introduction
Ocular surgical procedures are essential medical interventions for treating a wide range of visual disorders and improving patients’ quality of life. Among these, cataract surgery is one of the most common and effective procedures in ophthalmology [1]. Cataract is characterized by a progressive loss of crystalline lens transparency, resulting in blurred, cloudy, or distorted vision. If left untreated, it can cause substantial visual impairment or even blindness in severe cases. Phacoemulsification is the most widely used surgical technique for cataract extraction, offering rapid visual recovery and a low incidence of postoperative complications. It involves ultrasonic fragmentation and aspiration of the opacified crystalline lens through a small corneal incision, generally followed by implantation of an intraocular lens with minimal tissue disruption. Cataract surgery is currently considered a safe procedure, with a high success rate and rapid recovery [2]. Nevertheless, postoperative complications can occur, among which inflammation and infection require particular attention [3]. Ocular inflammation is an expected response to surgical tissue injury and forms part of the healing process, but it can cause discomfort and, when excessive or persistent, may impair vision or prolong recovery. A less frequent but potentially devastating complication is postoperative endophthalmitis, an intraocular infection generally involving the aqueous and/or vitreous humor [4]. Because of its potential to cause rapid and severe vision loss, postoperative endophthalmitis constitutes an ophthalmic emergency requiring immediate intervention [5,6]. To reduce the risk and clinical consequences of postoperative inflammation and infection, patients are often prescribed topical broad-spectrum antibiotics and corticosteroid anti-inflammatory agents during the postoperative period. Although topical therapy is generally effective when properly administered, its clinical performance depends on multiple factors, including patient adherence, correct instillation technique, ocular surface retention, precorneal drug loss, and variability in intraocular drug exposure. Frequent administration may complicate adherence, particularly among older patients or those who experience difficulties instilling eye drops. Sustained intraocular drug-delivery systems seek to reduce these sources of variability by providing controlled drug release directly at the intended site of action following surgery. In this study, we investigated a biodegradable intraocular implant intended for intracameral placement (BII), composed of a poly(lactic-co-glycolic acid) (PLGA) matrix and loaded with moxifloxacin hydrochloride (MOX HCl) and dexamethasone (DEX). The BII was developed to provide sustained release of both drugs while progressively disintegrating within the eye. Designed for placement in the anterior chamber during cataract surgery, the implant is intended to reduce dependence on postoperative eye-drop therapy. Combining antibiotic prophylaxis and anti-inflammatory treatment within a single intraoperative intervention may also simplify postoperative management and improve treatment standardization. The formulation development, manufacturing process, physicochemical characterization, in vitro release behavior, and initial exploratory assessment of the implant’s in vivo behavior were reported previously by our group [7]. The implant-disappearance and clinical-tolerability assessment and the 35-day IOP study included in the present work were conducted in new, independent cohorts to determine whether the findings previously observed during the exploratory in vivo evaluation could be reproduced. The animals, observations, and images reported here were not included in the previously published dataset. Beyond this repeat assessment, the present work addressed a distinct set of preclinical questions by evaluating anti-inflammatory activity in an experimental uveitis model, antibacterial performance following a low-inoculum bacterial challenge, and exploratory aqueous humor pharmacokinetics in aphakic and phakic eyes.
2. Materials and Methods
2.1. BII’s Production and Composition
In brief, the implants were produced by hot-melt extrusion using a Pharma 11 twin-screw extruder (Thermo Fisher Scientific, USA). A powder blend containing 50 % MOX HCl (Shreeji Pharma International, India), 10% DEX (Zhejiang Xianyu Pharmaceutical, China), and 40% PLGA Resomer RG502H (Evonik, Germany) was processed at 150 °C and a screw-rotation speed of 120 rpm. The polymer had a molecular weight range of 7,000–17,000 Da, an inherent viscosity of approximately 0.16 – 0.24 dL/g, and a lactide:glycolide ratio ranging from 48:52 to 52:48. The extruded fibers were manually cut under aseptic conditions to obtain cylindrical implants approximately 4 mm in length and 0.60 mm in diameter. The implants were subsequently sterilized by gamma irradiation at a dose of 30 kGy. Each implant had a target unit mass of 2 mg and contained nominal doses of 1 mg of MOX HCl and 0.20 mg of DEX. Unit mass, actual drug content, content uniformity, and physicochemical characterization were reported previously [7]. The implants used in the present experiments met the specifications established in that study. The implant dimensions were selected to satisfy several design requirements. The device had to accommodate the predetermined doses of MOX HCl and DEX while maintaining the mechanical integrity of the PLGA matrix. Because hot-melt extrusion was used, their cylindrical geometry was inherent to the manufacturing process: the final diameter was determined by the extrusion die, whereas the fiber length was adjusted to obtain the target unit mass and drug doses. From a surgical perspective, the selected dimensions represented a compromise between adequate handling with standard ophthalmic microsurgical instruments, minimization of implantation-related trauma, and placement within the anterior chamber through a corneal paracentesis. The effects of hot-melt extrusion and gamma irradiation on the physicochemical properties, drug stability, morphology, and in vitro release performance were comprehensively evaluated in the previous formulation-development study [7]. The resulting formulation remained compatible with the established quality and performance specifications. These assessments were therefore not repeated as study endpoints in the present work, which focused specifically on the in vivo preclinical evaluation of the implant.
2.2. Laboratory Animals
50 adult female 2.50 – 3.00 kg non-pregnant New Zealand White rabbits were included, contributing 56 eyes across six animal cohorts. Each rabbit was assigned to only one cohort and underwent only the experimental procedures corresponding to that cohort. Three rabbits contributed both eyes to the implant-disappearance and clinical-tolerability study. Five rabbits contributed one phakic BII-treated eye each to the 35-day IOP follow-up. Six rabbits contributed one aphakic BII-treated eye each to the short-term IOP study. 3 rabbits contributed both eyes to the paired uveitis experiment. Twenty-five rabbits contributed one eye each to the endophthalmitis study, and eight rabbits contributed one eye each to the pharmacokinetic study. For the secondary short-term IOP comparison, measurements from the five phakic BII-treated eyes belonging to the 35-day IOP cohort and the eight Pseudomonas aeruginosa-challenged BII-treated eyes from Group C of the endophthalmitis experiment were analyzed together with those from the six aphakic BII-treated eyes. Thus, no additional animals were used for this comparison. Formal random allocation was not performed. The eye represented the experimental unit in cohorts in which one eye per rabbit was evaluated. In the paired uveitis experiment, each eye represented an experimental unit, and the two eyes of the same rabbit constituted a matched pair. In the bilateral implant-disappearance and tolerability cohort, eyes were observational units nested within rabbits and were not treated as independent animals in inferential analyses. No specific strategy was used to counterbalance treatment order, measurement order, or cage location. Group allocation and experimental procedures were not masked. The ophthalmological examiner and the investigators conducting the data analyses were aware of group assignment. Complete masking of the ophthalmological examiner was not feasible because the implant was directly visible during slit-lamp examination. To reduce subjectivity, all assessments were performed using predefined clinical criteria under standardized examination conditions and were photographically documented. The absence of masking is acknowledged as a potential source of observer bias. No formal a priori inclusion or exclusion criteria were established for animals, experimental units, or data points.

Table 1.
Animal allocation, number of eyes, and experimental conditions for each study.
| Experiment | Rabbits | Eyes | Allocation |
|---|---|---|---|
| Implant disappearance Tolerability |
3 | 6 | Bilateral BII placement. The same cohort was followed throughout the study |
| 35-day IOP measurements | 5 | 5 | One phakic eye per rabbit received a BII and was monitored over the 35-day follow-up. Measurements obtained during the first six days were also included in the short-term IOP comparison. |
| Short-term IOP: Aphakia + BII | 6 | 6 | One eye per rabbit underwent phacoemulsification and received BII. These eyes were included in the short-term IOP comparison. |
| Uveitis | 3 | 6 | Bilateral phacoemulsification and LPS challenge. One eye received BII and the contralateral eye served as the matched control |
| Endophthalmitis | 25 | 25 | Group A: 6, Group B: 11, Group C: 8. One eye per rabbit. IOP measurements from the eight Group C eyes were also included in the short-term IOP comparison. |
| Pharmacokinetics | 8 | 8 | Aphakia + BII: 4 eyes, phakic eyes + BII: 4 eyes. One eye per rabbit |
All experiments were conducted in accordance with the guidelines of the Institutional Committee for the Care and Use of Laboratory Animals of the Facultad de Ciencias Médicas, Universidad Nacional de Córdoba (CICUAL–FCM–UNC), and the National Institutes of Health guidelines for the care and use of laboratory animals. The study protocol was approved in Resolution CE-2023-00288395. All rabbits were healthy at enrolment. They had not undergone previous experimental procedures before inclusion in the present study. Before the first session, animals were acclimatized to the animal facility for 1 week. No genetically modified animals were used. Rabbits were housed individually in numbered cages with environmental enrichment consisting of a wooden gnawing bar at the FCM–UNC animal facility, with 12-hour light/dark cycles. During clinical follow-up, the animals were monitored for overt behavioral signs compatible with pain or distress. Systemic anti-inflammatory analgesics were not routinely administered because they could interfere with the inflammatory endpoints of the study. Topical ketorolac was designated as rescue analgesia and was available if clinically required. All surgical procedures and serial aqueous-humor collections were performed under general and topical anesthesia conditions. General anesthesia was induced by intramuscular administration of ketamine (40 mg/kg) and xylazine (4 mg/kg), and topical anesthesia was provided using a proparacaine ophthalmic solution. The pupils were subsequently dilated with tropicamide ophthalmic solution, and an eyelid speculum was positioned to expose the ocular surface. All ophthalmological examinations, surgical procedures, and aqueous-humor collections were performed by an ophthalmologist. At completion of the assigned experimental protocol, or when a predefined humane endpoint was reached (overall clinical severity score > 9), the animals were anesthetized intramuscularly with a mixture of ketamine (40 mg/kg) and xylazine (4 mg/kg) and euthanized by gradual exposure to CO₂. Euthanasia was performed in a transparent acrylic chamber connected by a hose to a compressed CO₂ cylinder. The gas was introduced gradually, and exposure was continued until spontaneous respiratory movements had ceased. Death was confirmed by the absence of spontaneous respiration and heart sounds on auscultation, and absence of pupillary reactivity.
2.3. Intracameral BII Placement
The BII dimensions were selected to accommodate the target drug doses while allowing practical intracameral placement. Implantation was performed using ophthalmic microsurgical instruments under an operating microscope in a room equipped for animal surgery. After adequate general and topical ocular anesthesia had been confirmed, an approximately 1-mm peripheral, tunneled, self-sealing corneal incision (corneal paracentesis) was created at the limbus. The BII was then introduced through the paracentesis into the anterior chamber using curved, blunt-tipped ophthalmic forceps. Its free mobility within the anterior chamber was verified by gentle irrigation with sterile saline solution through a blunt cannula. Finally, self-sealing of the incision and complete reformation of the anterior chamber with the BII inside were confirmed. Weekly slit-lamp examinations were performed during the 35-day follow-up period to estimate changes in the apparent dimensions of the implant using the millimeter scale of the slit-lamp beam.
2.4. Endophthalmitis Model and Evaluation of BII-Associated Clinical Protection
25 rabbits were allocated without randomization to 3 experimental groups. No a priori sample-size calculation or prespecified allocation ratio was used, and the resulting comparisons were considered exploratory. At time zero, 60 µL of a suspension of Pseudomonas aeruginosa ATCC 27853 prepared in sterile saline (total inoculum of 6 – 8 CFU) was administered intravitreally [8]. The injection was performed using a 1 mL syringe fitted with a 30-gauge needle introduced transsclerally approximately 6 mm posterior to the corneal limbus. Before clinical signs of infection had developed, the animals received the following:
Group A: Intravitreal injection of 80 µL of sterile physiological saline (n = 6, control).
Group B: Intravitreal injection of 80 µL of a 2 mg/mL ceftazidime solution (n = 11).
Group C: Intracameral insertion of one BII (n = 8).
Clinical follow-up began on the day after inoculation and was scheduled to continue for six days, unless a predefined humane endpoint was reached. Because the interventions were administered before clinical disease establishment, the experiment was designed to assess prevention of clinical endophthalmitis following a nominal low-inoculum bacterial challenge rather than treatment of an ongoing infection. Clinical disease severity was evaluated using a predefined composite ophthalmic score developed for the present exploratory study. The anterior-chamber flare was graded using criteria adapted from the SUN recommendations [9], whereas conjunctival inflammation, corneal opacity, lens opacity, and post-tropicamide pupil diameter were assessed using the internal rubric shown below.
Table 2.
Composite clinical ophthalmic severity scoring rubric.
| A – Conjunctival inflammation | Score |
| None | 0 |
| Mild (scarce amount of injected and sectorized vessels) | 1 |
| Moderate (visualization of congestion in vessels in half of the ocular conjunctiva) | 2 |
| Severe (diffuse redness of the entire conjunctiva) | 3 |
| Critical (redness and edema of the entire conjunctiva) | 4 |
| B – Corneal opacity/keratitis | Score |
| No opacity nor keratitis | 0 |
| Opacity or diffuse keratitis, details of the iris clearly visible | 1 |
| Translucent areas easily distinguishable, details of the iris slightly darkened | 2 |
| Opalescent areas, no visible details of the iris, pupil size barely discernible | 3 |
| Opaque cornea, no discernible iris | 4 |
| C – Anterior-chamber inflammation (aqueous flare) | Score |
| None | 0 |
| Mild (slight opacity of the aqueous humor) | 1 |
| Moderate (opacity is present, but iris and lens are clearly identifiable) | 2 |
| Severe (iris and lens not clearly visible) | 3 |
| Critical (aqueous humor coagulation, iris and lens not visible, presence of fibrin) | 4 |
| D – Lens opacity | Score |
| None | 0 |
| Mild (opalescent zones, no difficulty to observe the posterior segment) | 1 |
| Moderate (major opalescent zones, but no difficulty to observe the posterior segment) | 2 |
| Severe (opacity level not allowing the observation of details from the posterior segment and the retina) | 3 |
| Critical (posterior segment not visible) | 4 |
| E – Post-tropicamide pupil diameter | Score |
| ≥ 8 mm | 0 |
| > 3 to < 8 mm | 1 |
| ≤ 3 mm | 2 |
| Overall clinical severity (A+B+C+D+E) | Score |
| Mild | 0-3 |
| Moderate | 4-6 |
| Severe | 7-9 |
| Critical | > 9 |
Individual domain scores were summed to obtain an overall clinical severity score ranging from 0 to 18, with higher values indicating more severe ocular involvement. The score was used as a clinical endpoint and was not intended to quantify viable intraocular bacterial burden or establish microbiological eradication. High-magnification digital photographs were obtained using a Canon EOS Rebel T6 camera mounted on the slit lamp to document the findings during examinations. For the statistical comparison between ceftazidime and BII-treated groups, the composite clinical severity scores recorded on each of the six follow-up days were averaged for each eye, resulting in one summary value per independent experimental unit. Because one eye per rabbit was evaluated, these per-eye summary values represented independent animals. Their distributions were compared between Group B (ceftazidime, n = 11 eyes) and Group C (BII, n = 8 eyes) using a two-sided Mann–Whitney test in Minitab 20.3. Group A was summarized descriptively and was not included in this inferential comparison because its animals reached the humane endpoint before completing the scheduled follow-up. A p value below 0.05 was considered statistically significant.
2.5. Exploratory Evaluation of BII’s Anti-Inflammatory Activity in Uveitis Model
Three rabbits underwent bilateral phacoemulsification [10]. After a 7–14-day recovery period and clinical resolution of the initial postoperative inflammation, both eyes of each rabbit received an intravitreal injection of 60 µL of a 1 ng/mL solution of lipopolysaccharide from Escherichia coli (LPS; Sigma-Aldrich, USA) to induce anterior uveitis [11]. During the same experimental session, one eye per rabbit additionally received a BII in the anterior chamber, whereas the contralateral eye underwent the same phacoemulsification and LPS challenge but did not receive a BII. Thus, each rabbit served as its own control, providing three matched pairs of eyes. Clinical examinations were performed daily by slit-lamp biomicroscopy throughout the four-day post-challenge follow-up period. Anterior-chamber inflammation was assessed by grading aqueous flare, visualized through the Tyndall phenomenon, according to the SUN scale from 0 (no flare) to 4 (intense flare) [9]. Assessments were performed at 16× magnification using a 3-mm slit beam positioned at a 45° angle, in a darkened room to optimize visualization. All examinations were documented with high-magnification digital photographs. Because only three matched pairs were available, individual paired trajectories and group-level results were summarized descriptively, without inferential statistical testing, and were considered hypothesis-generating.
2.6. Clinical Ophthalmological Examinations
Intraocular pressure (IOP) was measured in all study eyes using a digital rebound tonometer (iCare TonoVet, Finland). Measurements were obtained before each procedure, after complete recovery from general anesthesia when a postprocedural assessment was scheduled, and during follow-up examinations. Tonometry was always performed while the animals were fully conscious and without general anesthesia or sedation. Six consecutive readings were obtained from each eye, and their mean was recorded as the IOP value for that eye at the corresponding time point. The anterior segment was examined by slit-lamp biomicroscopy (Huvitz, South Korea) at 10× and 16× magnification. Direct unfiltered, indirect, and diffuse illumination modes were used as appropriate. When clinically indicated, vital staining and blue or green filters were employed to facilitate visualization of suspected ocular-surface lesions. The posterior segment was examined by binocular indirect ophthalmoscopy (Neitz, Japan) using a 20 D lens. When additional posterior-segment visualization was required, examination with a 90 D lens mounted on the slit lamp was also performed. Slit-lamp and funduscopic examinations were performed after pupil dilation with tropicamide and administration of topical ocular anesthesia. All ophthalmological assessments were conducted by an ophthalmologist, and relevant findings were documented using high-magnification digital photographs. At each examination time, the six consecutive tonometer readings were averaged to obtain a single visit-specific IOP value for each eye. For the long-term analysis, visit-specific IOP values from five phakic BII-treated eyes were evaluated at baseline and on days 1, 3, 7, 14, 21, 28, and 35. Temporal variation was assessed using the Friedman test, with time as the repeated factor and each eye identified as a block. Additional measurements from these eyes on days 2, 4, 5, and 6 were used only in the secondary short-term comparison and were not included in the long-term Friedman analysis. For the short-term analysis, visit-specific IOP values obtained on days 1 – 6 were averaged within each eye, yielding one summary value per experimental unit. The comparison included five phakic BII-treated eyes from the 35-day IOP cohort, eight Pseudomonas aeruginosa-challenged BII-treated eyes from Group C of the endophthalmitis experiment, and six aphakic BII-treated eyes. The resulting per-eye mean values were compared among the three experimental conditions with Kruskal–Wallis test. Pairwise comparisons were performed using Dunn’s post hoc test with Bonferroni adjustment for multiple comparisons. Baseline values were displayed descriptively but were not included in the per-eye means used. A p value below 0.05 was considered statistically significant. Across the clinical-score and IOP analyses, non-parametric methods were selected because of the small group sizes and, where applicable, the ordinal or repeated-measures structure of the data. Therefore, normality and homoscedasticity were not assumed. Independence or within-eye repetition was addressed by using one summary value per eye or by treating each eye as a block, as appropriate. Statistical analyses were performed using Minitab 20.3.
2.7. Aqueous Humor Collection for Pharmacokinetic Analysis
Eight rabbits contributed one study eye each and were divided into two cohorts. In the aphakic cohort (n = 4 eyes), the study eye underwent phacoemulsification and received a BII in the anterior chamber. In the phakic cohort (n = 4 eyes), one non-operated eye received a BII without prior phacoemulsification. Serial aqueous-humor samples were collected from the same study eye under general and topical ocular anesthesia by anterior-chamber paracentesis using a 30-gauge needle. Sampling was scheduled on days 1, 2, 3, 7, 10, 14, 17, and 24 after implantation. Samples were transferred to microcentrifuge tubes and stored at − 25 °C until processing. The volume collected ranged from 10 to 50 µL at each time point, depending on the amount that could be safely obtained under the ocular conditions present at the time of sampling. In some instances, no sample could be collected because ongoing inflammation prevented aqueous-humor aspiration. The exact volume of every collected sample was recorded before processing. Because sample volumes varied from 10 to 50 µL, a sample-specific dilution factor was calculated using the recorded initial volume and the volumes of all subsequently added solutions. The analytically measured concentrations were then back-calculated to obtain the corresponding concentrations in undiluted aqueous humor. When no sample could be collected, no concentration value was assigned for that time point. Such observations were recorded as missing and excluded from the analysis, whereas the remaining observations from the same eye were retained. Missing samples were not classified as concentrations below the limit of quantification. Information regarding all samples collected is available upon reasonable request.
2.8. Preparation and RP-HPLC Analysis of Aqueous Humor Samples
Depending on the volume of aqueous humor collected from each pharmacokinetic study eye (10 – 50 µL), 50 – 90 µL of a 50:50 (v/v) methanol/phosphate-buffer mixture was added to bring the initial preparation volume to 100 µL. The phosphate buffer was prepared by dissolving 2.72 g of KH₂PO₄ in 1 L of purified water containing 1 mL of triethylamine as a silanol-masking agent. Its pH was subsequently adjusted to 2.80 with phosphoric acid. A 100 µL volume of a mixed internal-reference solution was then added, resulting in a final processed-sample volume of 200 µL. The stock solution was prepared by dissolving 20 mg of sarafloxacin hydrochloride (SAR HCl, Career Henan Chemical Co., China) and 4 mg of beclomethasone (BEC, Shaanxi Dideu Medichem, China) in a mixture of 150 mL of dimethyl sulfoxide and 50 mL of 50:50 (v/v) methanol/phosphate buffer. A 5 mL aliquot of this stock solution was further diluted to 25 mL with 50:50 (v/v) methanol/phosphate buffer, yielding concentrations of 20 µg/mL for SAR HCl and 4 µg/mL for BEC. Following the 1:1 dilution produced by adding 100 µL of this solution to 100 µL of the aqueous-humor preparation, the final concentrations in the processed samples were 10 µg/mL for SAR HCl and 2 µg/mL for BEC. SAR HCl and BEC were used solely as internal process controls to verify the volumetric consistency of sample preparation. They were not used to normalize the MOX HCl or DEX peak areas because the diluted aqueous-humor samples showed adequate chromatographic separation without requiring an extraction step. Centrifugation was therefore not performed and the processed samples were analyzed directly. MOX HCl and DEX were quantified by single-point external-standard comparison using a combined mixed reference solution of 10 µg/mL MOX HCl and 2 µg/mL DEX. The suitability of single-point quantification was supported by the linear responses and negligible intercepts previously established for both analytes [7]. Concentrations in the processed samples were calculated by direct comparison with the corresponding external-standard peak areas and were corrected using the sample-specific dilution factor to express the results as concentrations in aqueous humor. Processed samples were analyzed in a Dionex Ultimate 3000 system (Thermo Fisher Scientific, USA) equipped with a BDS Hypersil C8 analytical column (250 × 4.6 mm, 5 µm, Thermo Fisher Scientific, USA). Chromatographic separation combined gradient and isocratic elution. The run was initiated with a 50:50 (v/v) methanol/phosphate-buffer mobile phase, which was linearly adjusted to 56:44 (v/v) over the first 5 min and then maintained isocratically until the end of the 10-min run. Detection was performed at 242 nm. The column temperature was maintained at 30 °C, the flow rate was 1.50 mL/min, and the injection volume was 20 µL. The underlying RP-HPLC method for the simultaneous quantification of DEX and MOX HCl had previously been validated for specificity, linearity, accuracy, precision, and instrumental limits of detection and quantification [7]. For the present analysis, the chromatographic conditions were adapted by introducing gradient elution and the two internal reference compounds described above. The adapted procedure was not subjected to a complete matrix-specific revalidation. System suitability under the modified chromatographic conditions was instead verified by evaluating peak separation, peak tailing factors, and the repeatability of standard-solution injections. Across five consecutive injections, peak tailing factors were below 2 and the RSD of individual peak areas did not exceed 0.73 %. SAR HCl and MOX HCl eluted within the 2.30 – 2.70 min retention window, whereas DEX and BEC eluted between 7 and 9 min.
2.9. Pharmacokinetic Evaluation
Concentration–time data obtained from aphakic and phakic eyes were analyzed by exploratory nonlinear mixed-effects modeling using Monolix® 2024 (Lixoft, France). Separate models were fitted for each drug and ocular condition. Because of the small number of animals in each group, ocular condition was not formally evaluated as a covariate. Candidate structural models incorporated first-order drug input from the implant and linear elimination, with one- or two-compartment structures evaluated according to the concentration–time profile of each drug. Structural models, residual-error models, and random-effects structures were compared using the Akaike information criterion (AIC), parameter precision expressed as relative standard error, goodness-of-fit plots, and visual predictive checks. All this data is available, and can be provided upon request. Random effects that could not be estimated with adequate precision were removed iteratively, considering both parameter precision and model fit. Concentrations below the lower limit of quantification (BLQ) were retained and treated as left-censored observations. For each BLQ record, the corresponding censoring limit was entered in the observation column and the record was identified using the Monolix CENSORING variable. These observations were incorporated into the likelihood during parameter estimation and were not replaced by zero or by an arbitrary numerical concentration. Samples that could not be collected were coded as missing and were distinguished from analytically censored observations. The instrumental LLOQ for MOX HCl was 0.15 µg/mL, and the censoring limits entered in Monolix were expressed on the same concentration scale as the corresponding observations. Because model observations were expressed as concentrations in undiluted aqueous humor, a sample-specific censoring limit was calculated as 0.15 × (200/VAH), where VAH was the collected aqueous-humor volume in microliters. The resulting censoring limits ranged from 0.60 to 3.00 µg/mL and were entered in Monolix on the same concentration scale as the Observations. After estimation of the final population parameters, 10,000 virtual concentration–time profiles were generated for each final model following a single BII placement using Simulx® 2024 (Lixoft, France). All simulations were performed from 0 to 30 days using an output interval of 0.10 days. These profiles were conditional model-based simulations derived from the fitted parameter distributions and should not be interpreted as independent experimental observations. Their purpose was to explore the implications of the preliminary pharmacokinetic models and to generate hypotheses for subsequent studies. Each simulated individual profile was subsequently analyzed by non-compartmental analysis using PK Analix® 2024 (Lixoft, France). The maximum concentration (Cmax) and the time to reach the maximum concentration (Tmax) were calculated for each virtual individual and summarized as median values across the simulated population.
3. Results and Discussion
3.1. Behavior and Tolerability Evaluation of the BII
The purpose of these observations was to evaluate the overall in vivo behavior of the implant, including its persistence within the anterior chamber, progressive visible disintegration, and disappearance over time, rather than to perform a formal quantitative morphometric analysis of its dimensions. The implant-disappearance and clinical-tolerability assessment was conducted in a new, independent cohort of three rabbits (six eyes) to determine whether the implant behavior and tolerability findings initially reported by our group [7] could be reproduced under comparable experimental conditions. The 35-day IOP assessment was conducted in a separate cohort and is reported below. The visible disintegration of the BII was qualitatively evaluated by slit-lamp examination at seven-day intervals. Consistent with the findings obtained in the previously published exploratory cohort [7], the implant showed progressive fragmentation and reduction in visible size. Visual estimates suggested an approximately 50 % reduction in visible implant size between successive weekly examinations during early follow-up. By weeks two to three, the reduction relative to the initially visible implant was approximately 80%. By the fourth week, no implant material could be identified by slit-lamp examination. This finding indicates complete visible disappearance from the anterior chamber under the examination conditions employed, but should not be interpreted as direct evidence of complete polymer degradation. Representative stages of this process are shown in Figure 1.
Although slit-lamp follow-up showed that no visible implant material remained after approximately four weeks, future studies incorporating histopathological evaluation are required to characterize possible tissue responses during and after the degradation process. No clinically detectable ocular damage was identified during serial biomicroscopic examinations. However, immediately after BII placement, transient whitish pseudomembrane-like material was observed in three of the six implanted eyes (50 %, Figure 2). The material progressively decreased in size and was no longer visible within several hours, whereas the implant itself remained identifiable during subsequent follow-up.
A possible explanation for this observation is the rapid hydration of the implant surface and an initial burst release of the highly water-soluble MOX HCl, which may have promoted the detachment or dispersion of material containing PLGA and poorly water-soluble DEX. Its subsequent disappearance could have involved dispersion within the aqueous humor, redistribution, partial drug dissolution, and/or clearance of the visible material. However, neither the composition of the pseudomembrane-like material nor the mechanism responsible for its formation and disappearance was experimentally determined; therefore, this interpretation remains hypothetical. Although this finding was observed in half of the implanted eyes, the small number of animals does not permit a precise estimation of its incidence. In all affected eyes, the material was transient, resolved spontaneously without therapeutic intervention, and was not accompanied by clinically detectable adverse effects during follow-up. It was considered clinically non-inflammatory in appearance because slit-lamp biomicroscopy revealed no concomitant conjunctival hyperemia, fibrin formation, progressive anterior chamber flare, or other signs consistent with active ocular inflammation. Nevertheless, this characterization was based exclusively on clinical examination, as histopathological and cytological analyses were not performed. Future studies should therefore include histological evaluation and/or aqueous-humor cytology to further elucidate the nature and biological significance of this transient finding. The present results do not allow its incidence or clinical relevance in humans to be predicted. Consequently, this phenomenon should be specifically investigated in subsequent preclinical studies and monitored in any future clinical evaluation.
3.2. BII’s Preclinical Performance in the Low-Inoculum Endophthalmitis Model
Following the nominal low-inoculum intravitreal challenge, the untreated challenged controls (Group A) showed a rapid increase in composite clinical severity scores, reaching the critical range by day 2. All six animals in this group reached the predefined humane endpoint and were therefore euthanized on day 2. In contrast, the group mean scores for the ceftazidime-treated eyes (Group B) and BII-treated eyes (Group C) remained within the low clinical-severity range throughout the six-day follow-up period. For the prespecified inferential comparison between Groups B and C, the clinical severity scores recorded from days 1 to 6 were averaged for each eye, yielding one summary value per experimental unit. No statistically significant difference was detected between the distributions of the per-eye mean scores in the ceftazidime and BII groups (two-sided Mann–Whitney test with n = 11 and n = 8 eyes, respectively, p = 0.28). Group A was not included in this inferential comparison because all animals reached the humane endpoint on day 2 and therefore did not contribute complete six-day follow-up data. The absence of a statistically significant difference between Groups B and C should not be interpreted as evidence of equivalence or non-inferiority. Furthermore, the composite score reflects clinical ocular involvement and does not provide a microbiological measurement of bacterial burden or eradication. The time-course profiles of the three groups are shown in Figure 3.
All six untreated challenged eyes in Group A developed rapidly progressive clinical signs consistent with severe experimental endophthalmitis. By day 2, immediately before euthanasia, these eyes exhibited abundant conjunctival discharge and inflammation, corneal opacity, marked anterior chamber turbidity, and loss of normal anterior-segment detail. In contrast, the eyes treated with ceftazidime (Group B) or BII (Group C) did not develop the progressive severe clinical presentation observed in Group A and retained a comparatively preserved anterior-segment appearance throughout the six-day follow-up period. Mild inflammatory findings were nevertheless observed in some Group B eyes, but these did not progress to clinical disease. Representative photographs are shown in Figure 4.
These observations concern the clinical manifestation of endophthalmitis and should not be interpreted as microbiological confirmation of bacterial eradication. The observed combination of clinical signs prevented visualization of relevant posterior-segment structures in Group A. Biomicroscopic examination revealed mild, nonprogressive alterations predominantly involving the cornea and conjunctiva in 4 of 11 eyes (36.4 %) from Group B and 1 of 8 eyes (12.5 %) from Group C. These findings were clinically compatible with changes associated with ocular manipulation, although their origin could not be conclusively established. The lower observed frequency in Group C may be compatible with an attenuation of inflammation by the DEX contained in the BII. Nevertheless, the proportions were evaluated descriptively, and the study was neither designed nor powered to determine whether this difference was attributable to DEX. Furthermore, the groups differed in both the composition and route of administration of their respective interventions. For the nominal low-inoculum bacterial challenge, 60 µL of a Pseudomonas aeruginosa suspension containing 1.0 – 1.3 × 10² CFU/mL were administered intravitreally, corresponding to a total inoculum of 6 – 8 CFU per eye. Other rabbit endophthalmitis models have used bacterial suspensions containing 1.0 × 10⁵ and 2.0 × 10⁵ CFU/mL, respectively [13,14]. Comparisons based exclusively on CFU/mL should, however, be interpreted cautiously because the total number of microorganisms administered also depends on the injection volume. These higher-inoculum models were designed to produce robust established disease for the evaluation of disease severity or therapeutic interventions. In contrast, the present experiment was designed to evaluate prophylactic performance following a low-level bacterial challenge, with ceftazidime or the BII administered before clinically apparent endophthalmitis had developed. The purpose of the selected inoculum was not to quantitatively reproduce the bacterial contamination occurring during human cataract surgery, which was not measured in the present study, but to model a low-inoculum contamination scenario relevant to prophylactic intervention. The use of a similarly low bacterial load is not unprecedented: another study [15] reported that an intravitreal inoculum of 5.50 ± 2.60 CFU of Pseudomonas aeruginosa consistently produced fulminant endophthalmitis in aphakic rabbit eyes. Although that study involved aphakic eyes, its findings demonstrate that a small number of intravitreally administered Pseudomonas aeruginosa organisms can be sufficient to induce severe ocular disease. A potential limitation of a low-inoculum model is the possibility of inconsistent disease induction. In the present experiment, however, all six untreated challenged eyes developed rapidly progressive clinical disease and reached the predefined humane endpoint by day 2. Thus, under the experimental conditions employed, the selected challenge was sufficient to produce a consistent severe clinical phenotype in the absence of antibiotic intervention. Conversely, the ceftazidime- and BII-treated groups maintained low clinical severity scores throughout follow-up. Because serial microbiological cultures or quantitative bacterial counts were not performed, these findings do not directly demonstrate bacterial proliferation in untreated eyes or microbiological eradication in treated eyes. Moreover, Group A was not included in the six-day inferential comparison because observations were unavailable after euthanasia. The contrast between Group A and the treated groups should therefore be interpreted descriptively. A related intraocular drug-delivery strategy was reported in another study [16], who developed a biodegradable, moxifloxacin-releasing membrane based on cross-linked hyaluronic acid. Unlike the rod-shaped BII evaluated in the present study, their device consisted of a thin, circular membrane measuring 5 mm in diameter. The authors reported sustained moxifloxacin concentrations in rabbit aqueous humor, maintenance of intraocular pressure, preservation of corneal structure, and antibacterial activity of ocular extracts against Pseudomonas aeruginosa and Staphylococcus aureus. However, their study did not include an intraocular bacterial-challenge experiment directly comparable to the present endophthalmitis model. Their findings therefore support the feasibility of sustained intraocular moxifloxacin delivery but should not be presented as independent confirmation of the preventive outcome observed here. Several sustained-release ocular drug-delivery platforms have been investigated, including intravitreal implants, injectable depots, hydrogels, microspheres, and nanoparticles [17]. These technologies differ substantially in their administration site, drug-loading capacity, release profile, biodegradation, and intended clinical indication. Many sustained-release ophthalmic systems have been developed primarily for posterior-segment diseases. In contrast, the present biodegradable implant was specifically conceived for placement in the anterior chamber during cataract surgery and combines an antibacterial and an anti-inflammatory agent within a single device. Its intended purpose is to provide sustained intraocular exposure while reducing reliance on repeated postoperative topical administration. Direct comparisons among these platforms should therefore be interpreted cautiously because they address different anatomical targets and therapeutic objectives. This design strategy reflects a broader evolution in ophthalmic pharmacotherapy, in which optimization of drug delivery is considered alongside the development of new therapeutic agents. By reducing the dependence of treatment performance on repeated patient-administered doses, sustained intraocular delivery may help control an important source of therapeutic variability: adherence. This is particularly relevant after cataract surgery, because topical treatment is frequently prescribed to older patients whose adherence may be affected by physical limitations, cognitive impairment, complex dosing regimens, medication costs, difficulty instilling eye drops, and incorrect administration. The combination of MOX HCl and DEX within a biodegradable intracameral implant therefore provides a clinical rationale that extends beyond the technological characteristics of the formulation itself.
3.3. Exploratory Preclinical Evaluation of BII’s Anti-Inflammatory Activity
The anti-inflammatory activity of the BII was evaluated using a paired experimental uveitis model in a total of three New Zealand White rabbits. The experiment was conducted exclusively in aphakic eyes. Both eyes of each rabbit received an intravitreal injection of a 1 ng/mL LPS solution; one eye additionally received an intracameral BII, whereas the contralateral eye served as the matched control without BII. Serial slit-lamp biomicroscopy showed descriptively lower mean anterior-chamber inflammation scores in BII-treated eyes than in their contralateral controls, with the greatest separation between conditions observed during the first two days after the LPS challenge. Inflammation in the BII-treated eyes approached baseline levels by day 3, and the group mean reached zero by day 4. In contrast, the control eyes showed a more gradual decrease and retained some degree of inflammation at the end of the four-day observation period. Because only three matched pairs of eyes were evaluated, no inferential statistical analysis was performed, and these findings should be interpreted as preliminary and hypothesis-generating.
Figure 5.
Time course of anterior-chamber inflammation following intravitreal LPS. Day 0 represents the baseline examination performed. The blue line represents LPS-challenged aphakic eyes without BII, whereas the red line represents the contralateral LPS-challenged aphakic eyes receiving an intracameral BII. Data correspond to three matched pairs of eyes from three rabbits and are presented as group means ± standard deviation. Because of the limited number of matched pairs used in this study, the results were analyzed descriptively and no inferential statistical comparison was performed.
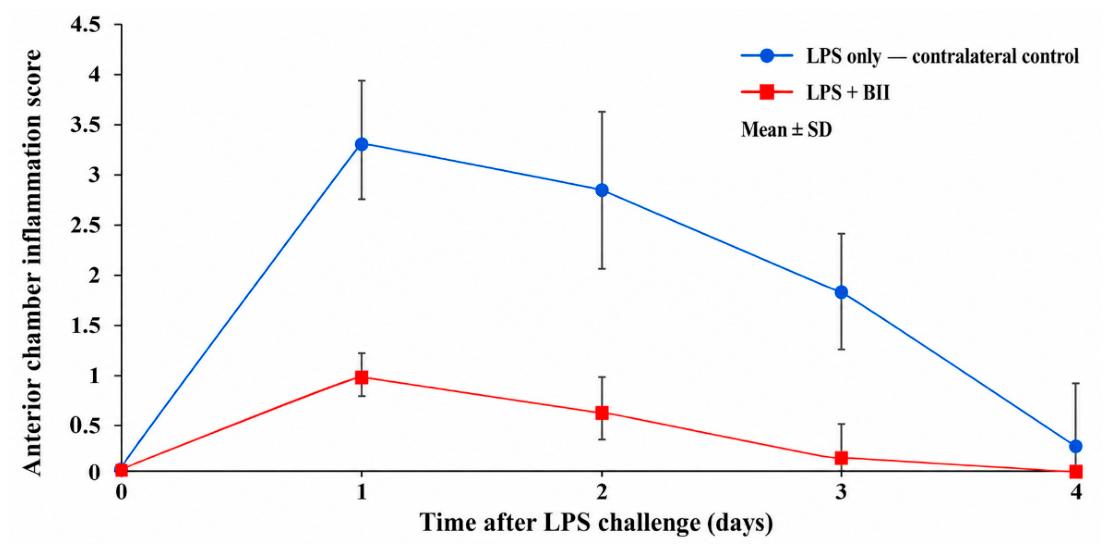
The uveitis experiment should be interpreted as a preliminary preclinical evaluation. Given the availability of only three matched pairs of eyes and the descriptive nature of the analysis, the findings cannot provide a precise estimate of the magnitude or variability of the anti-inflammatory effect. Nevertheless, at the group level, BII-treated eyes consistently showed lower mean inflammatory scores and faster clinical resolution than their matched untreated controls. Studies involving larger cohorts will therefore be required to confirm this preliminary observation. Anti-inflammatory activity has also been reported for another bioerodible PLGA implant containing DEX [18]. However, direct comparison with the present findings is limited by important differences in experimental design and device characteristics. In that study, rabbits underwent phacoemulsification with intraocular-lens implantation and received either one or two disc-shaped implants per eye. The devices measured 2.0 mm in diameter and approximately 1.5 mm in thickness and were sterilized with ethylene oxide before implantation. In contrast, the present study evaluated a rod-shaped BII after phacoemulsification and subsequent LPS challenge, without intraocular-lens implantation, and the implants were terminally sterilized by gamma irradiation at 30 kGy. These differences in ocular condition, implant geometry, formulation, and number of devices administered should be considered when comparing the results of the two studies. Slit-lamp examinations showed that anterior-chamber light scattering was most pronounced during the first days after LPS challenge, particularly in eyes without the BII. Breakdown of the blood–aqueous barrier increases the protein content of the aqueous humor, producing the clinical appearance known as flare. Under slit-lamp illumination, proteins and inflammatory cells suspended in the aqueous humor scatter the incident light, making the beam visible across the anterior chamber through the Tyndall phenomenon. Greater light scattering is therefore consistent with more intense anterior-chamber inflammation. Representative images illustrating the difference between LPS-challenged aphakic eyes with and without the BII for this study are presented in Figure 6.
3.4. Tonometry Evaluation
For the long-term IOP assessment, no statistically significant variation was detected across the follow-up times (Friedman test, n = 5 phakic BII-treated eyes, p = 0.072). Moreover, the longitudinal profile showed no sustained upward trend in IOP following BII placement. Raw data for the long-term IOP assessment is available upon request. In the short-term analysis, the per-eye mean IOP values differed significantly among phakic BII-only eyes (n = 5), Pseudomonas aeruginosa-challenged eyes receiving BII (n = 8), and aphakic eyes receiving BII (n = 6) (Kruskal–Wallis test, p = 2.20 × 10⁻³). Dunn’s post hoc test indicated that the aphakic BII-treated eyes had significantly lower mean IOP values than both the phakic BII-only eyes and the Pseudomonas aeruginosa-challenged BII-treated eyes, whereas no significant difference was detected between the latter two groups. The comparatively lower IOP observed in the aphakic group may reflect transient postoperative alterations in aqueous-humor dynamics associated with phacoemulsification. However, because aqueous-humor production and outflow were not independently evaluated, the mechanism underlying this difference cannot be determined from the present experiment. The daily IOP profiles for the three experimental conditions are shown in Figure 7.
By comparison, clinical studies evaluating Ozurdex, an intravitreal DEX implant, have reported ocular hypertension or clinically relevant IOP elevation in 18 –27 % of treated eyes, with higher rates described in patients with pre-existing glaucoma [19,20]. These findings provide relevant clinical context regarding the potential for corticosteroid-associated IOP elevation. However, direct comparison with the present results is limited by substantial differences in species, implantation site, DEX dose, clinical indication, and duration of follow-up. The Ozurdex polymer matrix dissolves gradually over several months, whereas no visible traces of the present intracameral BII remained approximately four weeks after implantation. Nevertheless, the absence of visible implant material does not necessarily demonstrate complete polymer degradation or termination of drug release. Therefore, although the shorter period of visible persistence could potentially limit the duration of corticosteroid exposure, the present findings do not establish a superior IOP safety profile relative to Ozurdex. The safety findings obtained in the present work should be interpreted within the scope of a preliminary preclinical study. Clinical ophthalmological examination, slit-lamp biomicroscopy, and IOP measurements were intended to detect clinically apparent ocular alterations during the observation period. No clinically detectable signs of ocular toxicity or sustained IOP elevation were identified using these methods. However, the small number of animals, the limited duration of follow-up, and the absence of microscopic tissue evaluation preclude definitive conclusions regarding ocular safety. Future studies incorporating larger cohorts, longer follow-up periods, corneal endothelial-cell assessment, and histopathological examination will be required to provide a more comprehensive characterization of the ocular safety profile.
3.5. Pharmacokinetic Modelling of DEX Concentrations
DEX concentration–time profiles were modelled separately for aphakic and phakic eyes receiving BII, with four animals included in each group. In both groups, the selected structural model was a two-compartment extravascular model without lag time, incorporating first-order input and linear elimination. Because DEX was delivered from an intracameral implant, ka should be interpreted as an effective first-order transfer rate from the implant depot into the central compartment rather than as a conventional extravascular absorption-rate constant. Interindividual variability was initially evaluated for all structural parameters (ka, CL, VD1, Q, and VD2 as shown below). Poorly estimated random-effect terms were removed through backward elimination. Decisions were based primarily on the RSE of the corresponding ω estimate while also considering the magnitude and plausibility of the estimated variability. At each step, AIC and model diagnostic plots were examined to ensure that removal of a random effect did not impair the overall model fit. All data regarding concentrations used for model fitting is available upon request.
Table 3.
Pharmacokinetic parameters for DEX.
| Parameter | Aphakic eyes + BII | Phakic eyes + BII |
|---|---|---|
| ka (days⁻¹) | 2.27 (RSE 69.3 %) | 1.82 (RSE 42.3 %) |
| VD1 (mL) | 66.17 (RSE 15.4 %) | 59.15 (RSE 10.5 %) |
| CL (mL/day) | 4 × 10⁻⁶ (RSE not estimable) | 4.86 (RSE 18.7 %) |
| Q (mL/day) | 9.02 (RSE 12.5 %) | 4.80 (RSE 20.5 %) |
| VD2 (mL) | 446.48 (RSE 17.4 %) | 88.95 (RSE 53.6 %) |
| ωVD1 | 0.28 (RSE 48.9 %) | - |
| ωQ | 0.15 (RSE 53.9 %) | - |
| ωCL | - | 0.17 (RSE 44 %) |
| Residual error | Proportional: 0.19 (RSE 15.5 %) | Proportional: 0.14 (RSE 15.7 %) |
For this formulation, ka should be interpreted as an effective transfer-rate constant describing the input of DEX from the implant into the aqueous humor rather than as a conventional extravascular absorption-rate constant, although the underlying mathematical representation is equivalent. The numerically higher ka estimated in aphakic eyes suggests that DEX transfer from the implant may have occurred more rapidly under this experimental condition. This behavior could plausibly reflect post-surgical changes in the ocular environment, including differences in implant hydration, contact with adjacent tissues, local permeability, and diffusional pathways. The absence of the crystalline lens may also facilitate redistribution between the anterior and posterior ocular spaces. Importantly, a higher ka is not incompatible with more extensive peripheral redistribution, because ka describes input from the implant into the modelled central compartment, whereas Q and VD2 describe subsequent exchange with the peripheral compartment. However, because ka was estimated with limited precision (RSE values were 69.3% and 42.3% in aphakic and phakic eyes, respectively) and the two groups were modelled separately using only four animals each, this interpretation should be regarded as a mechanistic hypothesis rather than as evidence of a confirmed difference between aphakic and phakic eyes. The similar VD1 estimates obtained for both groups suggest that the scaling of DEX concentrations within the modelled central compartment was not markedly altered by aphakia. In contrast, the higher point estimates of Q and VD2 in aphakic eyes are compatible with increased exchange between the central and peripheral model compartments and a greater apparent extent of peripheral distribution. Expressed as intercompartmental micro-rate constants, Q/VD1 was 0.14 and 0.08 days−1 in aphakic and phakic eyes, respectively, whereas Q/VD2 was 0.02 and 0.05 days−1. Thus, within the fitted model, aphakia was associated with a faster apparent transfer from the central to the peripheral compartment and a slower return from the peripheral to the central compartment. This pattern is compatible with a larger and more slowly equilibrating apparent peripheral reservoir in aphakic eyes, although it should be interpreted cautiously because VD2 was estimated with limited precision in the phakic group. Taken together, these estimates support the possibility that removal of the crystalline lens and the associated surgical alterations modified intraocular DEX disposition. Nevertheless, VD1 and VD2 represent apparent model volumes rather than anatomical ocular spaces, and Q represents modelled intercompartmental exchange rather than direct measurement of drug transport into a particular tissue. In particular, the VD2 estimate of 446.48 mL in aphakic eyes should not be interpreted as a physical ocular volume, but as an apparent scaling parameter potentially reflecting extensive tissue partitioning, local retention, or slow equilibration. These parameters may integrate several simultaneous processes, including implant dissolution, tissue permeation, local retention, redistribution, and incomplete or variable drug availability. Therefore, their biological interpretation remains plausible but cannot be assigned to a specific anatomical mechanism from the present data alone. In aphakic eyes, CL approached zero and its associated RSE could not be estimated, indicating that clearance was not independently identifiable from the available concentration–time data. Because the first sample was obtained 24 h after implantation, the initial DEX input phase was not directly characterized. Under these conditions, the model had limited information with which to separate transfer from the implant, distribution between model compartments, and elimination from the aqueous humor. Moreover, in a two-compartment model, disappearance from the central compartment may be attributed either to clearance or to transfer into the peripheral compartment followed by slow return. Consequently, parameter compensation among CL, Q, and VD2 may have contributed to the extremely low CL estimate. The resulting parameter pattern is compatible with a concentration–time profile governed predominantly by continued input from the implant and intraocular redistribution, with elimination contributing less information to the observed terminal phase. Thus, the extremely low CL estimate may reflect release or distribution-limited behavior within the fitted model. It should not, however, be interpreted as negligible physiological clearance of DEX from aphakic eyes. The pharmacokinetic models should be regarded as exploratory population models that provide an initial quantitative and biologically plausible description of intraocular DEX disposition. Despite the uncertainty associated with some individual parameters, the models adequately described the observed concentration–time profiles and provided a coherent framework for exploring the potential consequences of aphakia and for generating model-based simulations. Parameter precision and descriptive model performance represent related but distinct aspects of model evaluation: a parameter may be poorly identified even when the overall model captures the observed profiles adequately. In the present case, parameter uncertainty primarily limits the strength of the mechanistic interpretation and between-group comparison rather than eliminating the biological hypotheses suggested by the fitted model. The sampling schedule represented a compromise between pharmacokinetic characterization and animal welfare. Additional samples during the first postoperative hours would likely have improved characterization of DEX input from the implant and helped distinguish this process from distribution and elimination. However, repeated aqueous-humor collection would have required additional anesthesia and manipulation of recently operated eyes and could itself have modified the postoperative ocular environment. Future studies with larger cohorts and strategically distributed early sampling points will be useful for testing the mechanistic hypotheses generated by the present model and improving the identifiability of the corresponding parameters.
3.5.1. Populational Simulations for DEX
To explore the population-level concentration–time behavior predicted by the preliminary DEX models, the final parameter estimates obtained for both aphakic and phakic eyes were exported to Simulx®, the simulation module of the MonolixSuite®. For each experimental condition, 10,000 virtual individuals were simulated from the fitted population-parameter distributions. Simulations were performed from the time of BII placement through day 30 using an output interval of 0.10 day. These simulations were conditional on the corresponding fitted models and were intended to characterize the concentration–time behavior and interindividual variability implied by the experimental data. The 10,000 virtual profiles should not be interpreted as independent experimental observations or as an increase in the effective experimental sample size. The resulting median profiles and simulation-based percentile bands for aphakic and phakic eyes are presented in Figure 8. Both models predicted an early DEX concentration peak followed by a gradual decline over the 30-day simulation period. The aphakic model generated greater dispersion among the simulated profiles, particularly during the initial phase, consistent with the interindividual variability incorporated into its final parameter structure. These results describe the range of profiles supported by each fitted model and provide a basis for exploring potential differences in DEX disposition between aphakic and phakic eyes.
The simulations generated broader percentile bands for aphakic eyes than for phakic eyes, particularly during the initial post-implantation period, which also encompassed the predicted peak aqueous-humor concentrations. This pattern suggests that DEX exposure may be more variable under aphakic conditions. Such variability could plausibly reflect the combined effects of lens removal, early postoperative inflammation, and surgery-induced alterations in intraocular homeostasis, including changes in aqueous-humor dynamics, tissue permeability, and implant–tissue interactions. However, because the percentile distributions were conditional on separately fitted preliminary models, this interpretation should be regarded as a biologically plausible explanation rather than as a demonstrated causal effect of surgery. The 10,000 simulated concentration–time profiles generated for aphakic and phakic eyes were subsequently processed by non-compartmental analysis using PK Analix®. The distributions of the resulting pharmacokinetic parameters were summarized by their median values. For aphakic eyes, the median Cmax was approximately 2.50 µg/mL and the median Tmax was approximately 31 h after implantation. For phakic eyes, the corresponding median values were approximately 2.70 µg/mL and 36 h, respectively. These model-derived peak concentrations, equivalent to approximately 2500 and 2700 ng/mL, are substantially higher than the aqueous-humor DEX concentrations generally reported after topical ophthalmic administration, which typically fall within the tens to low hundreds of ng/mL depending on the formulation and dosing regimen [21]. Although differences in species, formulation, sampling design, and administration route preclude direct quantitative comparison, these findings support the capacity of intracameral BII placement to produce high local DEX exposure without dependence on corneal penetration. The simulated profiles also predicted sustained aqueous-humor exposure through day 30 in both aphakic and phakic eyes. The concentrations predicted at this time were within or close to the range in which DEX has demonstrated inhibition of inflammatory-mediator secretion in vitro [22]. This comparison supports the possibility that pharmacologically relevant DEX exposure may persist for approximately one month after BII placement. However, because no validated therapeutic concentration threshold has been established for DEX in rabbit aqueous humor, the simulations should not be interpreted as definitive evidence that therapeutic concentrations were maintained in every eye throughout the entire 30-day period. Rather, they provide model-based support for sustained anti-inflammatory exposure and a hypothesis to be evaluated in future studies.
3.6. Pharmacokinetic Modelling for MOX HCl
Because the ocular pharmacokinetics of the formulation were unknown when the study was designed, the sampling schedule was intended to cover both the expected initial input phase and the prolonged release period. However, MOX HCl concentrations declined below the LLOQ earlier than anticipated, limiting characterization of the terminal concentration–time profile. From Day 7 onward, most observations were non-detectable. The analytical method had an instrumental LLOQ of 0.15 µg/mL and an instrumental LOD of 0.05 µg/mL. Because no detectable chromatographic signal for MOX HCl was observed in these samples, the corresponding sample-specific censoring limits were derived from the LOD rather than from the LLOQ and were adjusted according to the dilution factor applied to each sample. Specifically, the censoring limit expressed in terms of the original aqueous-humor concentration was calculated as 0.05 µg/mL multiplied by the ratio between the final analytical volume of 200 µL and the volume of aqueous humor collected. Only one sample collected on Day 7 remained quantifiable, and no detectable signal for MOX HCl was observed in the subsequently collected samples through Day 24. Non-detectable observations were retained as left-censored data and incorporated into the likelihood during model estimation. These observations were not considered equivalent to zero and continued to constrain the concentration range. Although this approach allowed the information contained in samples to be retained, the small number of quantifiable concentrations necessarily increased uncertainty in the characterization of the terminal phase. Future studies should incorporate additional sampling points during the first postoperative days. The rapid decline in aqueous-humor concentrations may be related to the high aqueous solubility and hydrophilic character of MOX HCl. These physicochemical properties could favor its transport with aqueous-humor circulation while limiting prolonged retention or partitioning within lipophilic ocular tissues. This interpretation remains mechanistic, because drug elimination and tissue distribution were not measured independently in the present study. A one-compartment extravascular model without lag time, incorporating first-order input and linear elimination, was selected for both experimental conditions. As with DEX, ka represents an effective transfer-rate constant from the implant depot into the aqueous humor rather than a conventional absorption-rate constant. Because the MOX HCl model contained only three structural parameters (ka, VD, and CL shown below), all combinations of interindividual variability on these parameters were evaluated. The final model incorporated a proportional residual-error structure for aphakic eyes and a constant residual-error structure for phakic eyes. All data regarding concentrations used for model fitting is available upon request.
Table 4.
Pharmacokinetic parameters for MOX HCl.
| Parameter | Aphakic eyes + BII | Phakic eyes + BII |
|---|---|---|
| ka (days⁻¹) | 1.29 (RSE 55.80 %) | 2.19 (RSE 47.40 %) |
| VD (mL) | 43.61 (RSE 29.10 %) | 29.16 (RSE 13.10 %) |
| CL (mL/day) | 31.63 (RSE 20.10 %) | 20.73 (RSE 1.05 %) |
| ωka | - | 0.72 (RSE 43 %) |
| ωCL | 0.33 (RSE 33.85 %) | - |
| ωVD | - | 0.21 (RSE 56.60 %) |
| Residual error | Proportional: 0.44 (RSE 18.70 %) | Constant: 0.16 (RSE 17.70 %) |
The objective of this pharmacokinetic analysis was to obtain a preliminary quantitative description of MOX HCl release and disposition and to generate mechanistic hypotheses for subsequent studies with optimized sampling schedules. The point estimate of ka was approximately 70 % higher in phakic eyes than in aphakic eyes or, equivalently, approximately 41 % lower under aphakic conditions, suggesting that effective transfer of the drug from the implant into the aqueous humor may have occurred more slowly after lens removal. Nevertheless, ka was estimated with limited precision, with RSE values of 55.8 % and 47.4 % in aphakic and phakic eyes, respectively, and the initial input phase was not directly characterized because the first sample was obtained 24 h after implantation. Moreover, ka describes effective input from the implant depot into the modelled central compartment rather than subsequent redistribution from the aqueous humor toward other ocular structures. Therefore, the difference in ka should be regarded as an exploratory observation and should not be interpreted independently as evidence of either increased or decreased posterior redistribution. The apparent VD was about 1.5-fold higher, while CL was approximately 53 % higher under aphakic conditions. Collectively, these estimates are compatible with more extensive apparent distribution of MOX HCl following phacoemulsification, but they do not necessarily indicate faster terminal elimination. Indeed, VD and CL increased in nearly the same proportion: the VD/CL ratio remained almost constant in aphakic and phakic eyes (1.38 and 1.41 days, respectively), and the corresponding terminal elimination-rate constants, calculated as CL/VD, were also similar (0.72 and 0.71 days−1, respectively). Thus, removal of the crystalline lens did not appear to substantially modify the terminal elimination rate represented by the model. The higher apparent CL estimated in aphakic eyes is numerically consistent with the rapid decline in aqueous-humor concentrations and the predominance of non-detectable observations from day 7 onward, which were censored using sample-specific limits derived from the instrumental LOD of 0.05 µg/mL. However, the observed decline probably reflects the combined contributions of implant input, intraocular distribution, and elimination rather than clearance alone. In addition, the fraction of the released dose contributing to measurable aqueous-humor exposure was lower in aphakic eyes and was not estimated explicitly. Under this interpretation, the nearly proportional increases in VD and CL could arise from a lower apparent fraction of MOX HCl represented in the sampled aqueous-humor compartment rather than from independent increases in anatomical distribution volume and physiological clearance. Similarly, because VD and CL are apparent model parameters, their numerical values should not be interpreted as direct measurements of anatomical ocular volume or physiological aqueous-humor clearance. Taken together, the parameter estimates support the hypothesis that the crystalline lens and surrounding anatomical structures influence the intraocular disposition of MOX HCl, potentially acting as a partial barrier to drug redistribution or modifying local aqueous-humor dynamics. Following lens removal, changes in accessible intraocular space, fluid circulation, tissue contact, and diffusional pathways could contribute to a lower apparent fraction of MOX HCl remaining represented in the aqueous humor and to the observed differences in effective transfer rate, apparent distribution volume, and clearance. This effect may be particularly relevant for MOX HCl because of its greater hydrophilicity compared with DEX. Under clinical cataract-surgery conditions, implantation of an intraocular lens could produce a pharmacokinetic profile intermediate between, or otherwise distinct from, the aphakic and phakic conditions evaluated. Although the intraocular lens and remaining capsular structures may partially modify drug redistribution, they should not be assumed to reproduce the barrier and partitioning properties of the natural crystalline lens. Dedicated studies in pseudophakic eyes will be required to test this hypothesis and determine which of the present experimental conditions more closely approximates postoperative exposure.
3.6.1. Populational Simulations for MOX HCl
Following model evaluation, the final MOX HCl parameter estimates obtained for aphakic and phakic eyes were exported separately to Simulx®. For each experimental condition, 10,000 virtual individuals were simulated from the fitted population-parameter distributions. Simulations were performed from BII placement through day 30 using a time step of 0.10 day. These simulations were conditional on the preliminary models and were intended to characterize the concentration–time behavior and variability of the data rather than to represent additional observations. Both models generated an early MOX HCl concentration peak followed by a rapid decline below the analytical quantification limit. The greatest dispersion among the simulated profiles occurred during the initial post-implantation period, coinciding with the predicted peak concentrations. Appreciable early variability was observed in both experimental conditions, although its pattern differed between models. In aphakic eyes, this dispersion may partly reflect surgery-induced alterations in intraocular homeostasis and was represented in the final model by interindividual variability in CL together with a proportional residual-error structure. In phakic eyes, the simulated dispersion arose predominantly from the estimated interindividual variability in ka and VD, particularly the relatively large variability associated with VD. Consequently, the widths of the simulated percentile bands should be interpreted as model-implied variability from the specific parameter and residual-error structures selected. The present models cannot determine how much of this variability originated from biological differences, surgical effects, analytical variability, or parameter uncertainty. Nevertheless, simulations provide a useful representation of the range of early MOX HCl exposures supported by the experimental observations and identify the initial post-implantation period as the phase requiring the greatest sampling resolution in future studies.
Figure 9.
Model-based simulated concentration–time profiles for MOX HCl. Panel A shows simulations based on the model fitted to aphakic eyes receiving BII, whereas Panel B shows simulations based on the model fitted to phakic eyes receiving BII. The black line represents the median of 10,000 simulated individual profiles. The shaded regions represent successive percentile bands, with boundaries at the 5th, 20th, 35th, 50th, 65th, 80th, and 95th percentiles. These bands describe the distribution of simulated profiles conditional on the fitted population models and should not be interpreted as confidence intervals for the population median or as independent experimental observations.
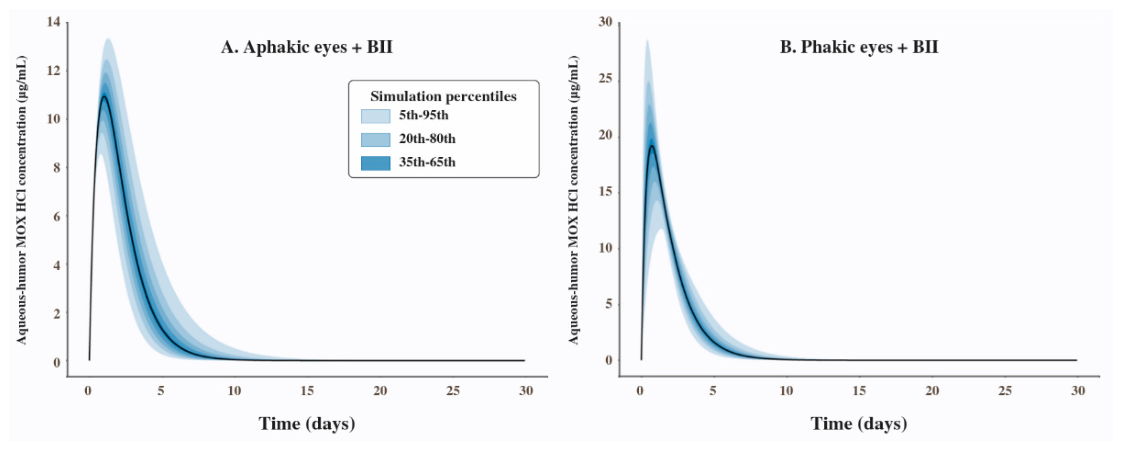
In the case of MOX HCl, population simulations were used to estimate the time intervals during which aqueous-humor concentrations exceeded selected MIC₉₀ benchmarks and could therefore be compatible with antibacterial activity. The selected model captured the main concentration–time pattern observed in vivo, including the very rapid decline in MOX HCl concentrations and the predominance of BLQ observations from day 7 onward. For aphakic eyes, PK Analix® indicated a median maximum concentration (Cmax) of approximately 10.94 µg/mL, reached at a Tmax of approximately 24 h. According to published susceptibility data [23], several bacterial species implicated in endophthalmitis exhibit MIC₉₀ values of 8 µg/mL or lower. Based on the median simulated profile for aphakic eyes, aqueous-humor concentrations exceeded the 8 µg/mL benchmark from approximately 9.60 to 51.60 h after implantation. For the lowest MIC₉₀ values considered, concentrations remained above the corresponding benchmark for more than five days. These intervals provide a descriptive comparison between the simulated exposure and published susceptibility data but should not be interpreted as definitive therapeutic windows. MIC₉₀ values represent population-level susceptibility estimates obtained in vitro and do not necessarily correspond to the susceptibility of an individual strain. Moreover, because the antibacterial activity of fluoroquinolones is concentration-dependent and is more closely associated with exposure indices such as Cmax/MIC and AUC/MIC, concentration–MIC comparisons alone do not establish antibacterial efficacy. The median simulated Cmax in aphakic eyes remained below the 16 µg/mL benchmark reported for some less susceptible isolates of Pseudomonas aeruginosa and Staphylococcus aureus. Accordingly, the aphakic median profile would not be expected to exceed this concentration. However, this observation should not be interpreted as evidence of insufficient activity against the Pseudomonas aeruginosa ATCC 27853 strain used in the present experiment, since its MIC was not experimentally determined and may differ from the published MIC₉₀ values obtained from collections of clinical isolates. Importantly, none of the BII-treated eyes showed clinical evidence of experimental endophthalmitis following the low-inoculum challenge. This finding is consistent with the implant providing sufficient antibacterial exposure to prevent clinically detectable disease under the specific experimental conditions evaluated. Nevertheless, because bacterial cultures, quantitative bacterial counts, and strain-specific susceptibility testing were not performed, microbiological eradication and the actual susceptibility of the challenge strain cannot be established. The simulations for phakic eyes showed narrower percentile bands than those obtained under aphakic conditions. Following analysis of the simulated profiles with PK Analix®, the median Cmax was estimated at approximately 19.52 µg/mL and was reached at a Tmax of approximately 19.20 h. Thus, compared with aphakic eyes, the phakic condition was associated with a higher median peak and an earlier Tmax. These differences suggest that lens status and the physiological alterations induced by the surgery may substantially influence the intraocular disposition of MOX HCl. Based on the phakic population median, aqueous-humor concentrations exceeded the 16 µg/mL benchmark from approximately 8.60 to 32.40 h after implantation. This result suggests that the implant may provide transient exposure above this relatively high susceptibility threshold, although it should not be interpreted as demonstrating coverage of all microorganisms with MIC₉₀ values at or above 16 µg/mL. From a prophylactic perspective, maintenance of antibiotic concentrations throughout the entire postoperative period is not necessarily required. In routine cataract surgery, intracameral antibiotics are commonly administered as a single dose at the end of the procedure to prevent bacterial establishment during the immediate perioperative period, when contamination is most likely to occur. Accordingly, the objective of the present implant was to provide intraocular antibiotic exposure during this early critical period rather than prolonged treatment of an established infection. The simulated exposure profiles, together with the absence of clinical endophthalmitis in BII-treated eyes, support the preliminary prophylactic potential of the implant under the low-inoculum conditions evaluated. The aphakic model does not reproduce the anatomical conditions of routine cataract surgery, in which an intraocular lens is implanted immediately after crystalline-lens extraction. Therefore, the pharmacokinetic profile observed in aphakic eyes should be interpreted as corresponding to a specific experimental condition rather than as a direct predictor of clinical exposure. It is plausible that pseudophakic eyes could display an intermediate pharmacokinetic behavior between the aphakic and phakic conditions for some parameters, owing to differences in ocular hydrodynamics, anatomical barriers, tissue distribution, and the presence of the intraocular lens. However, this remains a hypothesis that requires direct experimental evaluation. The aphakic model was selected because it provides a well-established platform for the preliminary investigation of postoperative intraocular inflammation and drug disposition. Future studies incorporating intraocular-lens implantation will be required to characterize the pharmacokinetic behavior and prophylactic performance of the implant under conditions more closely resembling routine cataract surgery.
4. Conclusions
In this work, a biodegradable intracameral implant based on PLGA and simultaneously loaded with DEX and MOX HCl was evaluated through a series of exploratory in vivo experiments involving rabbit models of aphakia, endotoxin-induced uveitis, and bacterial endophthalmitis. Under the conditions evaluated, the BII showed favorable clinical tolerability and pharmacological activity. Progressive disintegration was observed after implantation, and no visible implant material remained in the anterior chamber after approximately four weeks. No sustained elevation in IOP or other clinically detectable adverse ocular alterations were observed during follow-up. A transient pseudo-membrane developed shortly after implantation in approximately half of the implanted eyes. However, it resolved spontaneously within a few hours and was not accompanied by clinical signs of ocular inflammation. Because histopathological, cytological, and corneal endothelial evaluations were not performed, these findings should be interpreted as evidence of clinical tolerability rather than as a comprehensive demonstration of ocular safety. In the paired uveitis experiment, BII-treated eyes showed lower inflammatory scores and faster clinical resolution than their untreated contralateral controls. Given the limited number of matched pairs, these findings should be considered descriptive and hypothesis-generating. Following the low-inoculum challenge with Pseudomonas aeruginosa, untreated eyes rapidly developed critical endophthalmitis, whereas no clinical evidence of endophthalmitis was detected in BII-treated eyes. The distribution of per-eye mean clinical severity scores did not differ significantly between the BII- and ceftazidime-treated groups. Nevertheless, this result does not demonstrate therapeutic equivalence between the interventions, microbiological eradication, or universal protection against other bacterial strains, inoculum levels, or clinical scenarios. The exploratory pharmacokinetic models described distinct intraocular concentration–time profiles for DEX and MOX HCl. For DEX, the simulations predicted persistent aqueous-humor exposure through day 30, with median peak concentrations reached approximately 31 – 36 h after implantation. MOX HCl reached an earlier and higher peak, followed by a rapid decline, with most observations being below the quantification limit from day 7 onward. The median simulated profiles exceeded selected published MIC₉₀ benchmarks during the early period after implantation, particularly under phakic conditions. These concentration–MIC comparisons provide pharmacological context but should not be interpreted as definitive therapeutic windows or as evidence of activity against every microorganism represented by those susceptibility values. Differences between the aphakic and phakic models further suggest that lens status and surgery-associated changes in the ocular environment may influence the intraocular disposition of both drugs. Taken together, these findings provide preliminary proof-of-concept evidence supporting the BII as a potential intraoperative drug-delivery strategy intended to combine anti-inflammatory and antibacterial prophylaxis after cataract surgery. By delivering both drugs through a single biodegradable device, this approach could reduce dependence on postoperative eye-drop administration and simplify aftercare. However, the exploratory design, small experimental cohorts, absence of random allocation and complete masking, and lack of microbiological, histopathological, and corneal endothelial endpoints limit the conclusions drawn. Further studies involving larger cohorts, optimized pharmacokinetic sampling, strain-specific susceptibility testing, and pseudophakic models incorporating intraocular-lens implantation are required before the clinical safety and efficacy of the system can be established.
Author Contributions
The authors confirm contribution to the paper as follows: Conceptualization and design of study: PM, HP, LIT; Data collection: LJR, LM, LIT; Analysis and interpretation of results: PM, HP, AC, SDP, AWM, LIT; Drafting the manuscript: PM, LM, LJR, HP, LIT; All authors reviewed the results and approved the final version of the present manuscript.
Funding
This work was supported by scholarships POS_NAC_2018_1_151231 and POS_NAC_2022_1_174042 from Agencia Nacional de Investigación e Innovación (ANII, Uruguay) and scholarship BFPD_2025_1#45125453 from Comisión Académica de Posgrado (CAP, Uruguay).
Institutional Review Board Statement
We, the members of the Institutional Committee for Care and Use of Laboratory Animals of the Facultad De Ciencias Médicas UNC, have revised the manuscript entitled “Experimental Models of Prevalent Ocular Pathologies for the Evaluation of New Treatments” from Dr. Luis Ignacio Tártara in today’s general meeting (April 13th 2023). After our general evaluation we have verified that all rules established in the regulation have been respected, and therefore, we grant approval for this project (CE-2023-00288395).
Informed Consent Statement
Not applicable.
Data Availability Statement
Raw data can be requested via e-mail to the corresponding author.
Acknowledgments
We thank the Monolix developing team (Lixoft, France) for providing an academic license to use the Monolix Suite for pharmacokinetic modelling.
Conflicts of Interest
The authors declare that they have no known competing financial interests or personal relationships that could have appeared to influence the work reported in this paper.
Abbreviations
| ω | Interindividual variability |
| BII | Biodegradable intraocular insert |
| CL | Clearance (estimated in mL/day) |
| Cmax | Maximum concentration |
| DEX | Dexamethasone |
| FCM | Facultad de Ciencias Médicas |
| ka | Effective first-order transfer-rate constant from the implant (estimated in days-1) |
| MOX HCl | Moxifloxacin hydrochloride |
| PLGA | Poly(lactic-co-glycolic acid) |
| Q | Intercompartmental flow (estimated in mL/day) |
| RSE | Relative standard error |
| Tmax | Time of maximum concentration |
| UNC | Universidad Nacional de Córdoba |
| VD | Distribution volume for one-compartment models (estimated in mL) |
| VD1 | Distribution volume of the first compartment (estimated in mL) |
| VD2 | Distribution volume of the second compartment (estimated in mL) |
References
- Schuster, A. K.; Nickels, S.; Pfeiffer, N.; et al. Frequency of cataract surgery and its impact on visual function-results from the german gutenberg health study. Graefes Arch. Clin. Exp. Ophthalmol. 2020, 258(10), 2223–2231. [Google Scholar] [CrossRef]
- Scott, N. W.; Azuara-Blanco, A.; Solborg-Bjerrum, S.; et al. Epidemiology of 411140 cataract operations performed in public hospitals and private hospitals/clinics in Denmark between 2004 and 2012. Acta Ophthalmol. 2015, 93(1), 16–23. [Google Scholar] [CrossRef]
- Gogate, P.; Jaggernath, J.; Deshpande, S.; Naidoo, K. Meta-analysis to compare the safety and efficacy of manual small incision cataract surgery and phacoemulsification. Middle East Afr. J. Ophthalmol. 2015, 22, 362–369. [Google Scholar] [CrossRef]
- Shields, R. A.; Lee, I. J.; Brown, M. M.; et al. Clinical course and characteristics of eyes with recurrent episodes of endophthalmitis. Ophthalmol. Retin. 2020, 5(1), 10–15. [Google Scholar] [CrossRef]
- Dave, T. V.; Dave, V. P.; Sharma, S.; et al. Infectious endophthalmitis leading to evisceration: Spectrum of bacterial and fungal pathogens and antibacterial susceptibility. J. Ophthalmic Inflamm. Infect. 2019, 9(1). [Google Scholar] [CrossRef]
- Singh, R.; Davoudi, S.; Ness, S. Preventive factors, diagnosis, and management of injection-related endophthalmitis: A literature review. Graefes Arch. Clin. Exp. Ophthalmol. 2022, 260(8), 2399–2416. [Google Scholar] [CrossRef]
- Miranda, P.; Tártara, L.I.; Castro, A.; Zimet, P.; Faccio, R.; Palma, S.D.; Mombrú, Á.W.; Pardo, H. Sustained-release biodegradable intracameral implants containing dexamethasone and moxifloxacin: Development and in vivo primary assessment. Pharmaceutics 2025, 17, 1191. [Google Scholar] [CrossRef]
- Astley, R.A.; Coburn, P.S.; Parkunan, S.M.; Callegan, M.C. Modeling intraocular bacterial infections. Prog. Retin. Eye Res. 2016, 54, 30–48. [Google Scholar] [CrossRef]
- Jabs, D.A.; Nussenblatt, R.B.; Rosenbaum, J.T. Standardization of Uveitis Nomenclature (SUN) Working Group. Standardization of uveitis nomenclature for reporting clinical data: Results of the First International Workshop. Am. J. Ophthalmol. 2005, 140, 509–516. [Google Scholar] [CrossRef]
- Gurnani, B.; Mishra, D.; Kaur, K.; et al. Evolution of manual small-incision cataract surgery from 8 mm to 2 mm: A comprehensive review. Indian J. Ophthalmol. 2022, 70(11), 3773–3778. [Google Scholar] [CrossRef]
- Karaca, E.E.; Uzun, F.; Dileköz, E.; Öztürk Fincan, G.S.; Ercan, S.; Kul, O.; Bağrıaçık, E.Ü.; Or, M. The effect of endothelin receptor antagonists in the endotoxin-induced uveitis rabbit model. Cutan. Ocul. Toxicol. 2018, 37, 133–138. [Google Scholar] [CrossRef]
- Drikvandi, R. Non-linear mixed-effects models for pharmacokinetic data analysis: Assessment of the random-effects distribution. J. Pharmacokinet. Pharmacodyn. 2017, 44, 223–232. [Google Scholar] [CrossRef]
- Baba, R.; Umazume, K.; Koike, N.; et al. Study of the correlation between severity of endophthalmitis and posterior vitreous detachment using a rabbit endophthalmitis model. Invest Ophthalmol. Vis. Sci. 2022, 63(2). [Google Scholar] [CrossRef]
- Deniz, N.; Aydemir, O.; Güler, M.; et al. Comparison of efficiency of intravitreal ceftazidime and intravitreal cefepime in the treatment of experimental Pseudomonas aeruginosa endophthalmitis. Indian J. Ophthalmol. 2013, 61(9), 525–527. [Google Scholar] [CrossRef]
- Shockley, R.K.; Jay, W.M.; Fishman, P.H.; Aziz, M.Z.; Rissing, J.P. Effect of inoculum size on the induction of endophthalmitis in aphakic rabbit eyes. Acta Ophthalmol. (Copenh.) 1985, 63, 35–38. [Google Scholar] [CrossRef]
- Kim, D. J.; Jung, M. Y.; Park, J. H.; et al. Moxifloxacin releasing intraocular implant based on a cross-linked hyaluronic acid membrane. Sci. Rep. 2021, 11(1). [Google Scholar] [CrossRef]
- Mostafa, M.; Al Fatease, A.; Alany, R.G.; Abdelkader, H. Recent Advances of Ocular Drug Delivery Systems: Prominence of Ocular Implants for Chronic Eye Diseases. Pharmaceutics 2023, 15, 1746. [Google Scholar] [CrossRef]
- Chennamaneni, S. R.; Mamalis, C.; Archer, B.; et al. Development of a novel bioerodible dexamethasone implant for uveitis and postoperative cataract inflammation. J. Control Release 2013, 167(1), 53–59. [Google Scholar] [CrossRef]
- Chin, E. K.; Almeida, D. R. P.; Velez, G.; et al. Ocular hypertension after intravitreal dexamethasone (Ozurdex) sustained-release implant. Retina 2017, 37(7), 1345–1351. [Google Scholar] [CrossRef]
- Sweta, V. D.; Shibi-Dev, B. N.; Sandhya, R. Secondary glaucoma after intravitreal dexamethasone implant (Ozurdex) injection in patients with retinal disorder: A retrospective study. Indian J. Ophthalmol. 2022, 70(2), 585–589. [Google Scholar] [CrossRef]
- Weijtens, O.; Schoemaker, R. C.; Romijn, F. P.; et al. Intraocular penetration and systemic absorption after topical application of dexamethasone disodium phosphate. Ophthalmology 2002, 109(10), 1887–1891. [Google Scholar] [CrossRef]
- Nehmé, A.; Edelman, J. Dexamethasone inhibits high glucose, TNF-alpha-, and IL-1 beta-induced secretion of inflammatory and angiogenic mediators from retinal microvascular pericytes. Invest. Ophthalmol. Vis. Sci. 2008, 49, 2030–2038. [Google Scholar] [CrossRef]
- Miller, D. Review of moxifloxacin hydrochloride ophthalmic solution in the treatment of bacterial eye infections. Clin. Ophthalmol. 2008, 2(1), 77–91. [Google Scholar] [CrossRef]
Figure 1.
Representative slit-lamp images of the visible disintegration of the BII in vivo. Panels A, B, C, and D correspond to examinations performed during weeks one, two, three, and four after intracameral placement, respectively (n = 6 eyes). Progressive fragmentation and reduction in the visible size of the implant are shown in panels A – C. No implant material was identifiable by slit-lamp examination in panel D.
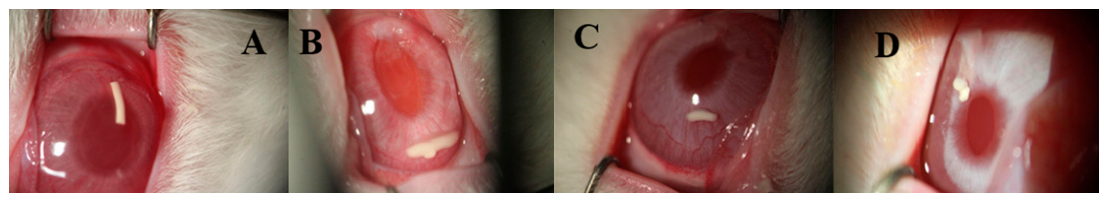
Figure 2.
Non-paired slit-lamp images of the pseudomembrane-like material. Panel A shows a BII-treated eye immediately after implantation, with the BII indicated by the solid arrow and the transient pseudomembrane-like material indicated by the dashed arrows. Panel B shows a different BII-treated eye after complete disappearance of the visible pseudomembrane-like material, with the BII remaining and clearly visible within the anterior chamber. The two panels were obtained from different animals and are presented as representative qualitative examples rather than as a longitudinal image sequence.
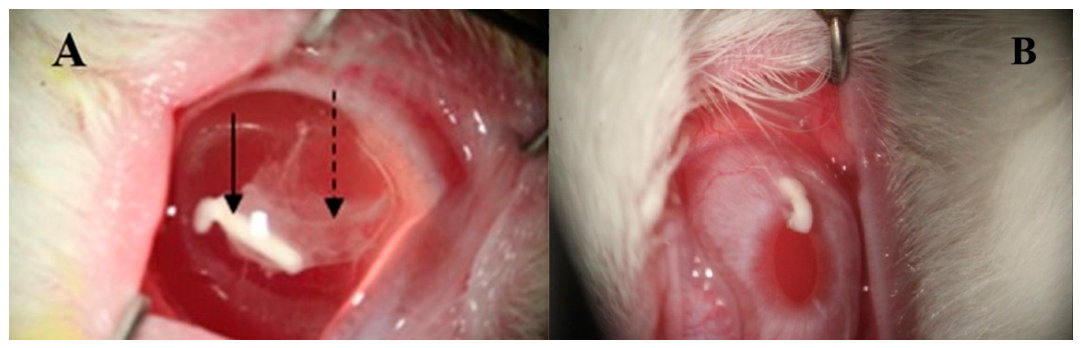
Figure 3.
Time course profiles of endophthalmitis composite clinical severity scores. Day 0 represents the baseline evaluation, and symbols represent the group mean at each follow-up time, with standard deviation bars. Group A (blue triangles; n = 6 eyes) comprised challenged eyes that received intravitreal saline without antibiotic treatment. Group B (red circles, n = 11 eyes) comprised challenged eyes treated with intravitreal ceftazidime, whereas Group C (yellow squares, n = 8 eyes) comprised challenged eyes receiving an intracameral BII. All six animals in Group A reached the predefined humane endpoint and were euthanized on day 2. Consequently, no subsequent observations were available for this group. The inferential comparison between Groups B and C was based on one mean clinical severity score per eye, calculated across days 1 – 6. No statistically significant difference was detected in this case (two-sided Mann–Whitney test, p = 0.28).
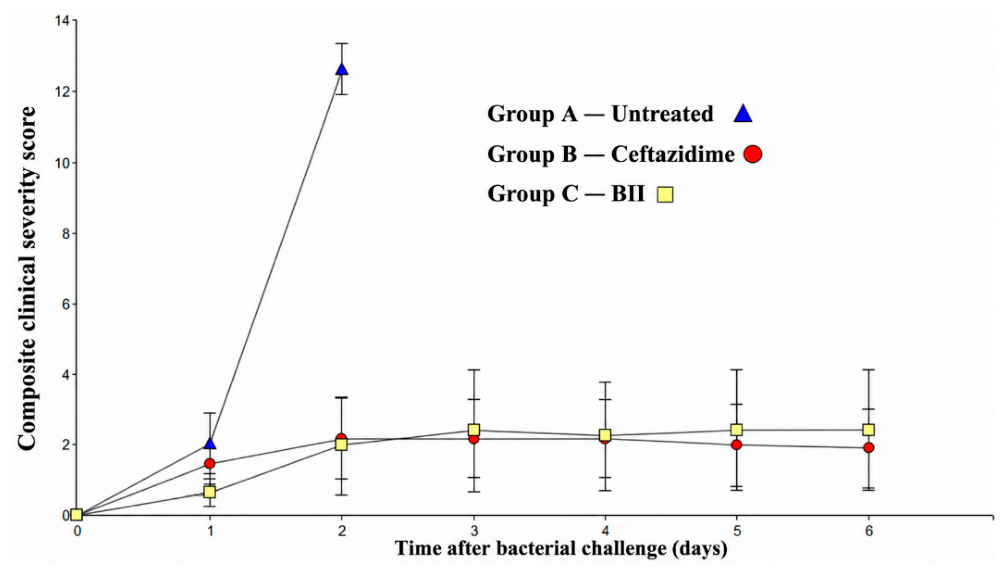
Figure 4.
Representative slit-lamp photographs of eyes in endophthalmitis experiment. Day 0 represents the baseline examination. Group A comprised untreated challenged controls and showed rapidly progressive conjunctival inflammation and discharge, corneal opacity, marked anterior chamber turbidity, and loss of normal anterior-segment detail by day 2. All animals in this group reached the predefined humane endpoint and were euthanized on day 2; consequently, no photographs were available from days 3 – 6. Group B received intravitreal ceftazidime, whereas Group C received an intracameral BII. Eyes in Groups B and C retained a comparatively preserved anterior-segment appearance during follow-up, although mild inflammatory findings were observed in some Group B eyes.
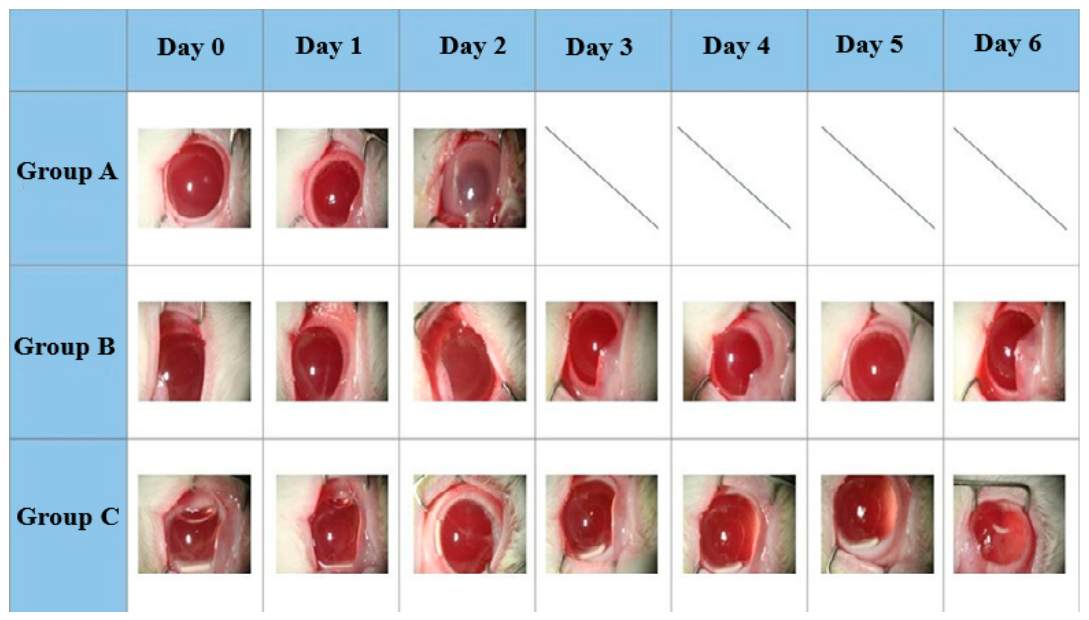
Figure 6.
Representative anterior-segment slit-lamp photographs after LPS challenge. Panels A1 – A4 correspond to LPS-challenged aphakic eyes without BII on days 1 – 4, respectively. Panels B1 – B4 correspond to LPS-challenged aphakic eyes receiving BII over the same observation period. The photographs illustrate the differences in anterior-chamber light scattering between the two experimental conditions. Inflammatory severity was assessed using the standardized clinical grading procedure described in Section 2.5.
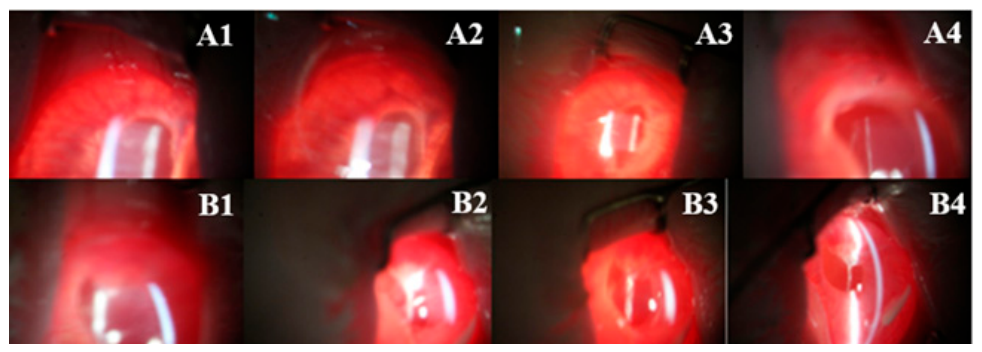
Figure 7.
Intraocular pressure during the six-day follow-up period. Bars represent mean IOP ± standard deviation at each observation time for control eyes (blue, n = 5 eyes), eyes challenged with Pseudomonas aeruginosa and receiving BII (red, n = 8 eyes), and aphakic eyes receiving BII (green, n = 6 eyes). For the inferential analysis, measurements obtained on days 1 – 6 were averaged for each eye, resulting in one summary value per experimental unit. The resulting means differed significantly among the three experimental conditions (Kruskal–Wallis test, p = 2.20 × 10⁻³). Dunn’s post hoc test indicated that the aphakic group differed significantly from both other groups, whereas no significant difference was detected between phakic BII-only eyes and Pseudomonas aeruginosa-challenged BII groups.
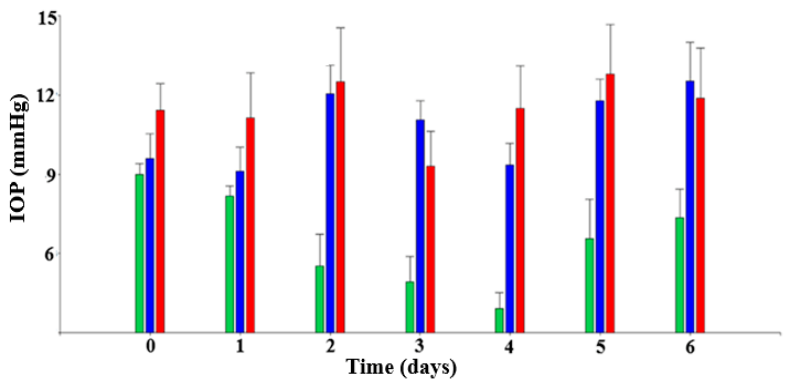
Figure 8.
Model-based simulated aqueous-humor concentration–time profiles for DEX. Panel A shows simulations based on the model fitted to aphakic eyes receiving BII, whereas Panel B shows simulations based on the model fitted to phakic eyes receiving BII. The black line represents the median of 10,000 simulated individual profiles. The shaded regions represent successive percentile bands, with boundaries at the 5th, 20th, 35th, 50th, 65th, 80th, and 95th percentiles. These bands describe the distribution of simulated profiles conditional on the fitted population models and should not be interpreted as confidence intervals for the population median or as independent experimental observations.
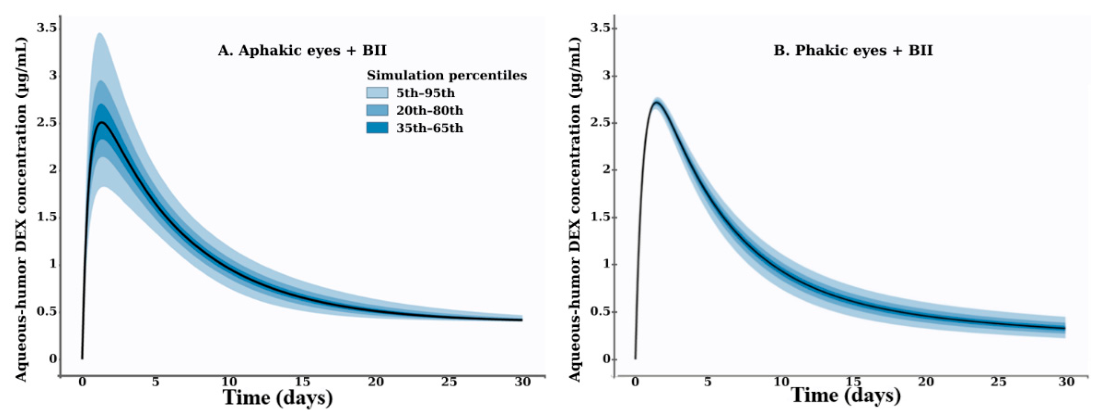
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.