

Submitted:
30 September 2026
Posted:
02 October 2026
You are already at the latest version
Abstract
Objective: To assess whether the systemic immune-inflammation index (SII), neutrophil-to-lymphocyte ratio (NLR), platelet-to-lymphocyte ratio (PLR), AST-to-platelet ratio index (APRI) and fibrosis-4 (FIB-4) score, derived from first-trimester tests, discriminate intrahepatic cholestasis of pregnancy (ICP) and predict adverse perinatal outcomes within ICP. Materials and Methods: This retrospective case–control study included 115 women with ICP and 64 healthy controls. Indices were derived from 11–14-week values. The composite adverse outcome comprised preterm birth, meconium-stained amniotic fluid, fetal distress, neonatal intensive care admission or a 1-minute Apgar score <7. ROC analysis with DeLong comparisons and logistic regression adjusted for age and body mass index were used. Results: APRI (p < 0.001), NLR (p = 0.002) and SII (p = 0.011) were higher in ICP; FIB-4 was similar. Among derived markers, APRI had the highest area under the curve (AUC 0.786; 95% CI 0.718–0.851); however, ALT alone performed better (AUC 0.895; DeLong p = 0.003), and APRI and SII added nothing to ALT (AUC 0.904; p = 0.465). In the adjusted model, APRI (OR 3.36 per 0.1 unit; 2.16–5.25) and SII (OR 1.45 per 100 units; 1.08–1.96) remained independent. Within the ICP group, no index predicted adverse outcomes; only serum bile acids did (AUC 0.754; OR 2.39 per 10 µmol/L; 1.54–3.69), which persisted, though attenuated, after excluding the protocol-driven preterm component (AUC 0.681). Conclusion: First-trimester APRI and SII carry an early hepatocellular–inflammatory signal in women who later develop ICP, but add no diagnostic value beyond transaminases and do not predict perinatal risk; surveillance and delivery timing should continue to rely on bile acids.
Keywords:
intrahepatic cholestasis of pregnancy
; systemic immune-inflammation index
; APRI
; FIB-4
; bile acids
; preterm birth
1. Introduction
Intrahepatic cholestasis of pregnancy (ICP) is the most common pregnancy-specific liver disorder and typically presents in the late second or third trimester with pruritus without rash, elevated serum bile acids, and variable elevation of transaminases. Its prevalence varies markedly between populations, ranging from 0.5% to 1.5% in most European populations and reaching higher rates in South American and Scandinavian populations (1). The pathogenesis is multifactorial: against a background of genetic susceptibility conferred by variants in genes encoding bile salt transporters (ABCB4, ABCB11, ATP8B1, NR1H4), the rising concentrations of estrogen and progesterone metabolites in advancing gestation impair hepatocellular bile transport; this is accompanied by endoplasmic reticulum stress, mitochondrial dysfunction, alterations in extracellular matrix regulation and activation of immune–inflammatory pathways (2). ICP is therefore regarded not as a purely cholestatic condition but as a complex process in which hepatocellular injury and a systemic inflammatory response coexist.
Although the maternal course of ICP is largely benign, the fetal risks are considerable. Spontaneous preterm birth, meconium-stained amniotic fluid, fetal distress, neonatal intensive care unit (NICU) admission and, at the most severe end, stillbirth are recognized consequences of the disease. Large meta-analyses based on individual patient data show that these risks are not evenly distributed and that stillbirth risk increases significantly only when total serum bile acids exceed 100 µmol/L (3). Current guidelines therefore recommend basing the diagnosis on serum bile acid measurement and tailoring the intensity of surveillance and the timing of delivery to bile acid concentrations (4). This approach, however, carries an inherent delay: bile acids are measured only after pruritus has developed, results may take several days in many centres, and risk stratification can therefore be undertaken only once the disease is already established. An inexpensive, widely available marker applicable in early pregnancy could fill this gap and would have clear clinical value.
Composite indices derived from the complete blood count have been widely studied in obstetric research in recent years because they reflect the systemic inflammatory balance more comprehensively than individual cell counts. Foremost among these is the systemic immune-inflammation index (SII), which integrates neutrophil, platelet and lymphocyte counts (5). Similarly, the aspartate aminotransferase-to-platelet ratio index (APRI) and the fibrosis-4 (FIB-4) score, developed for the non-invasive assessment of liver injury and fibrosis, are simple tools calculable from routine laboratory data that have gained acceptance in hepatology as alternatives to biopsy (6). In ICP, these indices have mostly been examined at diagnosis, that is, in the third trimester, whereas the information they may carry in the first trimester, before the disease becomes clinically apparent, remains largely unexplored. In this study, we aimed to determine both the diagnostic value of SII, neutrophil-to-lymphocyte ratio (NLR), platelet-to-lymphocyte ratio (PLR), APRI and FIB-4, calculated from first-trimester blood counts and liver tests obtained during routine antenatal care, in distinguishing ICP from healthy pregnancies, and their predictive value for adverse perinatal outcomes among women with ICP.
2. Materials and Methods
2.1. Study Design and Ethical Approval
This single-center, retrospective case–control study was approved by the Non-Interventional Clinical Research Ethics Committee of İzmir City Hospital (date:22.07.2026, decision no. 2026/442), and all procedures were performed in accordance with the principles of the Declaration of Helsinki. Because of the retrospective design and the use of anonymized hospital records, the ethics committee waived the requirement for individual informed consent. The study is reported in accordance with the 22-item Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) checklist for case–control studies (7).
2.2. Setting and Participants
The study population comprised women who received antenatal care at the Perinatology Clinic of İzmir City Hospital and delivered at the same center. The hospital information management system and archived records were reviewed retrospectively between 25 August and 24 September 2026, covering women who delivered between 1 January 2024 and 5 May 2026. ICP was diagnosed in the presence of otherwise unexplained pruritus and a fasting total serum bile acid concentration of ≥10 µmol/L; elevated transaminases were recorded as supportive findings (4,8). We enrolled all women with ICP who met the diagnostic criteria consecutively. The control group was selected by simple random sampling from women who delivered during the same period, had no pruritus, had liver function tests within reference limits in the first trimester and throughout pregnancy, and had no diagnosis of liver disease; cases and controls were not matched. All controls had first-trimester AST and ALT values of ≤31 U/L.
Exclusion criteria for both groups were multiple pregnancy; known chronic liver disease (viral hepatitis, autoimmune hepatitis, primary biliary cholangitis, cirrhosis or gallstone disease); pre-eclampsia, HELLP syndrome or acute fatty liver of pregnancy; pre-gestational diabetes, chronic hypertension, chronic kidney disease, hematological disease or malignancy; active infection or inflammatory disease; use of corticosteroids, immunosuppressive or anti-inflammatory drugs during pregnancy; unavailable first-trimester laboratory data; and incomplete delivery records. Figure 1 summarises the participant selection process.
2.3. Variables and Definitions
Recorded demographic and obstetric variables were age, gravidity, parity and body mass index (BMI). BMI was calculated as weight measured at the first antenatal visit divided by height squared. Laboratory variables comprised the complete blood count (neutrophil, lymphocyte and platelet counts) and liver function tests (AST and ALT) obtained from blood samples drawn at the routine first-trimester screening visit at 11–14 weeks of gestation. Total serum bile acids were measured in a fasting sample obtained at diagnosis, before initiation of ursodeoxycholic acid, and were used to grade disease severity in the ICP group.
Adverse perinatal outcomes were defined a priori. Preterm birth was defined as delivery before 37 weeks of gestation; meconium-stained amniotic fluid as the presence of meconium in the amniotic fluid at delivery; fetal distress as a category II/III intrapartum fetal heart rate pattern requiring urgent intervention; and NICU admission as admission of the neonate to the intensive care unit within the first 24 hours after birth. The composite adverse perinatal outcome was defined as the presence of at least one of preterm birth, meconium-stained amniotic fluid, fetal distress, NICU admission or a 1-minute Apgar score <7. Disease severity was classified according to serum bile acid concentration as mild (<40 µmol/L), moderate (40–99 µmol/L) or severe (≥100 µmol/L) (3,8). According to institutional protocol, delivery is planned at 37 weeks of gestation in women with ICP, and earlier delivery is decided on an individualised basis in women with serum bile acids ≥40 µmol/L; a substantial proportion of preterm births in this series were therefore iatrogenic, which must be considered when interpreting the results. Because the mode of labour onset (spontaneous labour, induction or planned caesarean section) was not systematically recorded, preterm births could not be classified as spontaneous or iatrogenic. As the use of the ≥40 µmol/L bile acid threshold for both severity grading and timing of delivery renders the association between bile acids and preterm birth partly definitional, a second composite outcome excluding the preterm birth component (meconium-stained amniotic fluid, fetal distress, NICU admission or 1-minute Apgar score <7) was examined as a sensitivity analysis.
2.4. Calculation of Indices
All indices were calculated from first-trimester laboratory values using the following formulae:
NLR = neutrophil count / lymphocyte count
PLR = platelet count / lymphocyte count
SII = (neutrophil count × platelet count) / lymphocyte count (5)
APRI = [AST (U/L) / upper limit of normal for AST (40 U/L)] × 100 / platelet count (10⁹/L) (6)
FIB-4 = [age (years) × AST (U/L)] / [platelet count (10⁹/L) × √ALT (U/L)] (9)
The AST/ALT (De Ritis) ratio, which reflects the pattern of hepatocellular injury, was also calculated. All blood counts were measured on an automated haematology analyser and biochemical parameters by standard autoanalyser methods in the same central laboratory.
2.5. Outcome Measures
The primary outcome was the diagnostic performance of first-trimester indices in distinguishing ICP from healthy pregnancies. Secondary outcomes were the predictive value of the same indices for the composite adverse perinatal outcome, preterm birth and NICU admission among women with ICP, and the association of the indices with disease severity and serum bile acid concentration. The composite outcome excluding the preterm birth component was evaluated as a sensitivity analysis.
2.6. Control of Bias
To minimize selection bias, we enrolled all women with ICP who met the diagnostic criteria. Data were extracted independently by two investigators using a standardized data collection form, and discrepancies were resolved by reference to the source records. Laboratory values were recorded according to a predefined time window (11–14 weeks) and separately from outcome data. Because BMI differed significantly between groups, all perinatal outcome analyses were repeated using logistic regression models adjusted for BMI and age to control for potential confounding.
2.7. Sample Size
Because all eligible women during the study period were included, no a priori sample size calculation was performed. Instead, the sensitivity of the available sample was assessed in terms of the smallest detectable effect using the Hanley–McNeil approach: with α = 0.05 (two-sided), the sample of 115 cases and 64 controls had approximately 93% power to distinguish an area under the curve (AUC) of 0.65 from 0.50. For the predictive analyses within the ICP group (52 events vs. 63 non-events), power was approximately 80% for an AUC of 0.65 and approximately 45% for an AUC of 0.60; these analyses are therefore insufficient to exclude small effects. Post hoc power analysis was not performed, as it merely re-expresses the observed p-values.
2.8. Statistical Analysis
Data were analysed using SPSS version 27.0 (IBM Corp., Armonk, NY, USA); bootstrap confidence intervals for ROC curves, DeLong tests, variance inflation factor (VIF) calculations and figures were produced with Python 3.11 (SciPy, statsmodels, scikit-learn and matplotlib libraries). Normality of continuous variables was assessed with the Shapiro–Wilk test; descriptive statistics are presented in the tables as both mean ± standard deviation and median (interquartile range). For two-group comparisons, Welch’s t test was used for variables normally distributed in both groups and the Mann–Whitney U test otherwise; the Kruskal–Wallis test was used for three-group comparisons, with Bonferroni-corrected pairwise comparisons where the overall test was significant. Categorical variables are presented as n (%) and were compared using the chi-square, Fisher’s exact or Fisher–Freeman–Halton tests. Effect sizes are reported as Cohen’s d for continuous variables and as odds ratios (OR) with 95% confidence intervals (CI) for categorical variables. The between-group difference in birth weight was re-examined using linear regression adjusted for gestational age at delivery (ANCOVA).
Diagnostic and predictive performance was evaluated using receiver operating characteristic (ROC) curves; 95% CIs for AUCs were computed with 4000 bootstrap replicates, and AUCs derived from the same subjects were compared using the DeLong test. Optimal cut-off values were determined by the Youden index, at which sensitivity, specificity, positive predictive value (PPV), negative predictive value (NPV) and accuracy were calculated. Because PPV and NPV depend on the proportion of ICP in the sample (64.2%), these values were additionally recalculated for a population prevalence of 1% using Bayes’ theorem. The incremental diagnostic contribution of the derived indices beyond transaminases was tested by adding APRI and SII to a model containing ALT alone, using the likelihood ratio test and AUC comparison. Correlations between continuous variables were assessed with Spearman’s rank correlation coefficient (ρ). Covariates in the multivariable logistic regression models were specified a priori: age, BMI, APRI and SII for the model of ICP presence, and bile acids, APRI, SII, age and BMI for the perinatal outcome models within the ICP group. Because NLR is a mathematical component of SII, it was not entered into the main models; models including NLR and alternative models including all variables with p < 0.20 in univariable analysis were fitted as sensitivity analyses. Multicollinearity was assessed with the VIF (VIF > 5 considered problematic), and model fit with Nagelkerke R². A p value < 0.05 was considered statistically significant for all tests.
3. Results
3.1. Characteristics of the Study Population
Of the 142 women identified with ICP on record review, 27 (19.0%) with missing first-trimester laboratory data or delivery records were excluded (Figure 1). Consequently, 115 women with ICP and 64 healthy pregnant women without liver disease selected by simple random sampling were included in the analysis, giving a total study population of 179. The groups were similar in age (29.97 ± 5.28 vs. 29.05 ± 5.27 years; p = 0.469), gravidity (2.05 ± 1.06 vs. 2.11 ± 1.13; p = 0.827) and parity (0.83 ± 0.85 vs. 0.64 ± 0.74; p = 0.172). In contrast, BMI was significantly lower in the ICP group (29.03 ± 3.12 vs. 30.34 ± 3.36 kg/m²; p = 0.004); BMI was therefore included as a potential confounder in subsequent models (Table 1, Panel A). No stillbirths occurred in either group, and all neonates had a 1-minute Apgar score ≥5.
3.2. Laboratory Parameters and Systemic Inflammatory/Fibrosis Indices
As expected, transaminases were markedly higher in the ICP group: AST 27.2 ± 10.6 vs. 17.9 ± 5.8 U/L (p < 0.001) and ALT 37.8 ± 25.8 vs. 14.1 ± 3.8 U/L (p < 0.001). Accordingly, the AST/ALT (De Ritis) ratio was significantly lower in the ICP group (0.87 ± 0.39 vs. 1.34 ± 0.53; p < 0.001), which was interpreted as indicating predominantly ALT-driven hepatocellular injury in ICP. First-trimester ALT exceeded 40 U/L in 41 women with ICP (35.7%), whereas no control exceeded 31 U/L.
Among systemic inflammatory markers, neutrophil count (6.61 ± 1.57 vs. 6.03 ± 0.45 ×10⁹/L; p = 0.026), NLR (3.29 ± 0.81 vs. 2.96 ± 0.85; p = 0.002) and SII (735.7 ± 149.0 vs. 699.4 ± 88.9; p = 0.011) were significantly higher in the ICP group. Lymphocyte count (p = 0.130), platelet count (p = 0.170) and PLR (p = 0.455) did not differ between groups. Among the liver fibrosis indices, APRI was markedly higher in the ICP group (0.307 ± 0.133 vs. 0.190 ± 0.078; p < 0.001), whereas FIB-4 did not differ significantly (0.63 ± 0.24 vs. 0.60 ± 0.31; p = 0.104) (Table 1, Panel C; Figure 3). In terms of effect size, APRI showed a large difference (Cohen’s d = 1.01), whereas NLR (d = 0.40) and SII (d = 0.28) showed small-to-moderate differences.

Table 1.
Demographic, obstetric and laboratory characteristics of the ICP and control groups.
| Variable | ICP (n = 115) | Control (n = 64) | p |
|---|---|---|---|
| A. Demographic and obstetric characteristics | |||
| Age (years) | 30.0 ± 5.3 30.0 (26.0–33.0) |
29.0 ± 5.3 29.0 (25.0–34.0) |
0.469 |
| Gravidity | 2.1 ± 1.1 2.0 (1.0–3.0) |
2.1 ± 1.1 2.0 (1.0–3.0) |
0.827 |
| Parity | 0.8 ± 0.9 1.0 (0.0–1.0) |
0.6 ± 0.7 1.0 (0.0–1.0) |
0.172 |
| Body mass index (kg/m²) | 29.0 ± 3.1 28.4 (27.0–30.5) |
30.3 ± 3.4 30.1 (28.6–32.0) |
0.004 |
| B. Laboratory parameters | |||
| AST (U/L) | 27.2 ± 10.6 25.0 (19.5–33.0) |
17.9 ± 5.8 17.0 (13.0–21.2) |
<0.001 |
| ALT (U/L) | 37.8 ± 25.8 33.0 (20.5–45.5) |
14.1 ± 3.8 13.0 (12.0–15.0) |
<0.001 |
| AST/ALT ratio | 0.87 ± 0.39 0.83 (0.62–0.97) |
1.34 ± 0.53 1.27 (0.93–1.64) |
<0.001 |
| Platelets (×10⁹/L) | 230.0 ± 47.3 230.0 (196.0–254.0) |
253.8 ± 76.2 226.0 (194.5–311.2) |
0.170 |
| Neutrophils (×10⁹/L) | 6.61 ± 1.57 6.37 (5.63–7.48) |
6.03 ± 0.45 6.00 (5.80–6.20) |
0.026 |
| Lymphocytes (×10⁹/L) | 2.07 ± 0.50 1.98 (1.67–2.50) |
2.17 ± 0.52 1.98 (1.94–2.70) |
0.130 |
| C. Derived inflammatory and fibrosis indices | |||
| NLR | 3.29 ± 0.81 3.20 (2.80–3.66) |
2.96 ± 0.85 2.96 (2.24–3.18) |
0.002 |
| PLR | 114.6 ± 25.9 115.2 (94.9–131.0) |
116.4 ± 16.0 115.0 (106.1–126.9) |
0.455 |
| SII (×10⁹/L) | 735.7 ± 149.0 747.8 (638.0–851.2) |
699.4 ± 88.9 686.7 (655.5–750.2) |
0.011 |
| APRI | 0.307 ± 0.133 0.285 (0.218–0.376) |
0.190 ± 0.078 0.178 (0.127–0.238) |
<0.001 |
| FIB-4 | 0.63 ± 0.24 0.60 (0.47–0.72) |
0.60 ± 0.31 0.53 (0.40–0.70) |
0.104 |
In each cell, the upper line shows mean ± standard deviation and the lower line median (interquartile range). Because no continuous variable was normally distributed in both groups according to the Shapiro–Wilk test, all comparisons were performed with the Mann–Whitney U test. ICP: intrahepatic cholestasis of pregnancy; NLR: neutrophil-to-lymphocyte ratio; PLR: platelet-to-lymphocyte ratio; SII: systemic immune-inflammation index (neutrophils × platelets / lymphocytes); APRI: AST-to-platelet ratio index; FIB-4: fibrosis-4 index. p < 0.05 was considered significant.
3.3. Perinatal Outcomes
Gestational age at delivery was significantly lower in the ICP group (36.6 ± 0.9 vs. 38.0 ± 1.4 weeks; p < 0.001), as was birth weight (2929.3 ± 336.4 vs. 3190.0 ± 366.3 g; p < 0.001). The 1-minute Apgar score was significantly lower in the ICP group (7.57 ± 0.59 vs. 7.78 ± 0.58; p = 0.002), although the clinical relevance of this difference was limited, as the proportion with an Apgar score <7 was similar in the two groups (4.3% vs. 4.7%; p = 1.000). However, the difference in birth weight disappeared after adjustment for gestational age at delivery (adjusted difference −26 g; 95% CI −130 to 78; p = 0.620) and remained unchanged after further adjustment for age and BMI (−37 g; p = 0.495), indicating that the lower birth weight in the ICP group largely reflected earlier delivery.
With regard to categorical perinatal outcomes, the rate of preterm birth was approximately twice as high in the ICP group (33.9% vs. 15.6%; OR 2.77; 95% CI 1.27–6.03; p = 0.009). Meconium-stained amniotic fluid was numerically more frequent in the ICP group (13.9% vs. 6.3%), but the difference was not statistically significant (p = 0.119). Rates of fetal distress (13.9% vs. 10.9%; p = 0.569) and NICU admission (23.5% vs. 23.4%; p = 0.995) were similar between groups. The composite outcome, defined as the presence of at least one adverse perinatal outcome, occurred in 45.2% of the ICP group and 32.8% of controls, a difference that did not reach statistical significance (OR 1.69; 95% CI 0.89–3.20; p = 0.106) (Table 2).
In view of the BMI difference between groups, logistic regression models adjusted for BMI and age were fitted for all perinatal outcomes. Effect sizes were virtually unchanged after adjustment: the adjusted OR was 2.71 (95% CI 1.23–6.00; p = 0.014) for preterm birth and 1.56 (95% CI 0.81–3.01; p = 0.182) for the composite adverse outcome. Results were likewise unchanged for meconium-stained amniotic fluid (adjusted OR 2.26; p = 0.171), fetal distress (adjusted OR 1.15; p = 0.781) and NICU admission (adjusted OR 0.93; p = 0.856). BMI was not an independent predictor in any model (all p > 0.15) (Table 5, Panel D).
Table 2.
Perinatal outcomes by group.
| Variable | ICP (n = 115) | Control (n = 64) | OR (95% CI) | p |
|---|---|---|---|---|
|
A. Continuous variables (mean ± SD median (IQR)) | ||||
| Gestational age at delivery (weeks) | 36.6 ± 0.9 37.0 (36.3–37.0) |
38.0 ± 1.4 38.0 (37.0–39.0) |
— | <0.001 |
| Birth weight (g) | 2929.3 ± 336.4 2950.0 (2750.0–3120.0) |
3190.0 ± 366.3 3175.0 (2972.5–3412.5) |
— | <0.001 |
| 1-minute Apgar score | 7.6 ± 0.6 8.0 (7.0–8.0) |
7.8 ± 0.6 8.0 (8.0–8.0) |
— | 0.002 |
| B. Categorical outcomes, n (%) | ||||
| Preterm birth (<37 weeks) | 39 (33.9) | 10 (15.6) | 2.77 (1.27–6.03) | 0.009 |
| Meconium-stained amniotic fluid | 16 (13.9) | 4 (6.3) | 2.42 (0.77–7.59) | 0.119 |
| Fetal distress | 16 (13.9) | 7 (10.9) | 1.32 (0.51–3.39) | 0.569 |
| NICU admission | 27 (23.5) | 15 (23.4) | 1.00 (0.49–2.06) | 0.995 |
| 1-minute Apgar score <7 | 5 (4.3) | 3 (4.7) | 0.92 (0.21–4.00) | 1.000 |
| Composite adverse perinatal outcome | 52 (45.2) | 21 (32.8) | 1.69 (0.89–3.20) | 0.106 |
The composite adverse perinatal outcome was defined as the presence of at least one of the following: preterm birth (<37 weeks), meconium-stained amniotic fluid, fetal distress, NICU admission or 1-minute Apgar score <7. Odds ratios were calculated by crude (unadjusted) logistic regression and p values were obtained from the chi-square or Fisher’s exact test; minor discrepancies between confidence intervals and p values may therefore occur in borderline cases. OR: odds ratio; CI: confidence interval; NICU: neonatal intensive care unit.
3.4. Diagnostic Performance of the Indices in Discriminating ICP
On ROC analysis, ALT showed, as expected, the best discrimination between ICP and controls (AUC 0.895; 95% CI 0.844–0.940; p < 0.001; cut-off ≥20 U/L, sensitivity 75.7%, specificity 96.9%). Among the derived markers, APRI (AUC 0.786; 95% CI 0.718–0.851; p < 0.001) and the AST/ALT ratio (AUC 0.787; 95% CI 0.714–0.854; p < 0.001) performed best, with nearly identical values. At a cut-off of ≥0.245, APRI had a sensitivity of 67.0%, specificity of 79.7%, PPV of 85.6% and accuracy of 71.5%; the AST/ALT ratio provided the same discrimination in the opposite direction (≤0.977: sensitivity 75.7%, specificity 73.4%). By the DeLong test, the AUC of ALT was significantly higher than that of APRI (p = 0.003); APRI did not differ from the AST/ALT ratio (p = 0.993) or AST (p = 0.867), but discriminated significantly better than SII (p = 0.004) and NLR (p = 0.001). The PPV of 85.6%, which depends on the proportion of ICP in the sample (64.2%), falls to 3.2% at an assumed population prevalence of 1%, with an NPV of 99.6%.
The discriminative ability of the inflammatory indices was statistically significant but clinically weak: AUC 0.642 (95% CI 0.555–0.726; p = 0.001) for NLR and 0.615 (95% CI 0.534–0.696; p = 0.005) for SII. The AUCs for FIB-4 (0.573; p = 0.115) and PLR (0.466; p = 0.435) did not differ significantly from 0.5 (Table 4, Panel A; Figure 2A). When the incremental contribution of the derived indices beyond transaminases was tested, adding APRI and SII to a model containing ALT alone modestly improved model fit (likelihood ratio test p = 0.032) but did not significantly improve discrimination (AUC from 0.895 to 0.904; DeLong p = 0.465).
3.5. Predictors of Adverse Perinatal Outcome in Women with ICP
Within the ICP group, women with (n = 52; 45.2%) and without (n = 63; 54.8%) the composite adverse perinatal outcome did not differ significantly in any inflammatory or fibrosis index: NLR (3.18 ± 0.62 vs. 3.38 ± 0.93; p = 0.504), SII (710.6 ± 147.9 vs. 756.4 ± 147.8; p = 0.101), APRI (0.303 ± 0.143 vs. 0.311 ± 0.125; p = 0.527) and FIB-4 (0.68 ± 0.29 vs. 0.60 ± 0.19; p = 0.230). In contrast, serum bile acids were markedly higher in women with an adverse outcome (45.6 ± 35.1 vs. 22.9 ± 8.0 µmol/L; p < 0.001). These women also delivered earlier (36.0 ± 1.1 vs. 37.0 ± 0.2 weeks; p < 0.001) and had lower birth weights (2786.4 ± 371.9 vs. 3047.1 ± 251.1 g; p < 0.001) (Table 3, Panel A).
Table 3.
Subgroup analyses within the ICP group: composite adverse perinatal outcome and disease severity.
Table 3.
Subgroup analyses within the ICP group: composite adverse perinatal outcome and disease severity.
| Variable | Adverse outcome (n = 52) | No adverse outcome (n = 63) | p |
|---|---|---|---|
| A. Comparison by presence of the composite adverse perinatal outcome | |||
| Age (years) | 30.9 ± 5.8 31.0 (26.0–35.0) |
29.2 ± 4.8 28.0 (26.0–33.0) |
0.096 |
| BMI (kg/m²) | 29.1 ± 3.0 28.4 (26.9–30.1) |
29.0 ± 3.2 28.4 (27.0–30.8) |
0.917 |
| Bile acids (µmol/L) | 45.6 ± 35.1 34.0 (23.0–49.5) |
22.9 ± 8.0 21.0 (17.0–28.0) |
<0.001 |
| AST (U/L) | 26.7 ± 11.8 23.5 (18.0–33.0) |
27.6 ± 9.5 26.0 (21.0–33.5) |
0.321 |
| ALT (U/L) | 35.6 ± 26.5 26.0 (18.0–43.0) |
39.6 ± 25.2 35.0 (22.5–46.0) |
0.104 |
| Platelets (×10⁹/L) | 227.0 ± 44.8 219.5 (197.8–247.8) |
232.5 ± 49.5 235.0 (194.0–260.5) |
0.529 |
| NLR | 3.18 ± 0.62 3.21 (2.81–3.54) |
3.38 ± 0.93 3.20 (2.80–3.75) |
0.504 |
| PLR | 115.2 ± 23.7 119.3 (97.9–129.0) |
114.0 ± 27.7 105.9 (93.0–132.4) |
0.428 |
| SII (×10⁹/L) | 710.6 ± 147.9 739.8 (620.6–824.9) |
756.4 ± 147.8 761.4 (684.4–865.8) |
0.101 |
| APRI | 0.303 ± 0.143 0.278 (0.224–0.364) |
0.311 ± 0.125 0.301 (0.218–0.386) |
0.527 |
| FIB-4 | 0.68 ± 0.29 0.60 (0.50–0.78) |
0.60 ± 0.19 0.60 (0.46–0.68) |
0.230 |
| Gestational age at delivery (weeks) | 36.0 ± 1.1 36.0 (36.0–36.9) |
37.0 ± 0.2 37.0 (37.0–37.0) |
<0.001 |
| Birth weight (g) | 2786.4 ± 371.9 2805.0 (2600.0–3000.0) |
3047.1 ± 251.1 3000.0 (2900.0–3200.0) |
<0.001 |
3.7. Disease Severity Subgroups According to Serum Bile Acids
Based on serum bile acids, women were classified as having mild (<40 µmol/L; n = 93; 80.9%), moderate (40–99 µmol/L; n = 16; 13.9%) or severe (≥100 µmol/L; n = 6; 5.2%) disease. NLR (p = 0.816), SII (p = 0.349), APRI (p = 0.083) and FIB-4 (p = 0.054) did not differ significantly across severity groups; only ALT increased with severity (35.4 ± 24.7, 40.1 ± 19.8 and 69.2 ± 38.1 U/L; p = 0.024; Bonferroni-adjusted p = 0.043 for mild vs. severe).
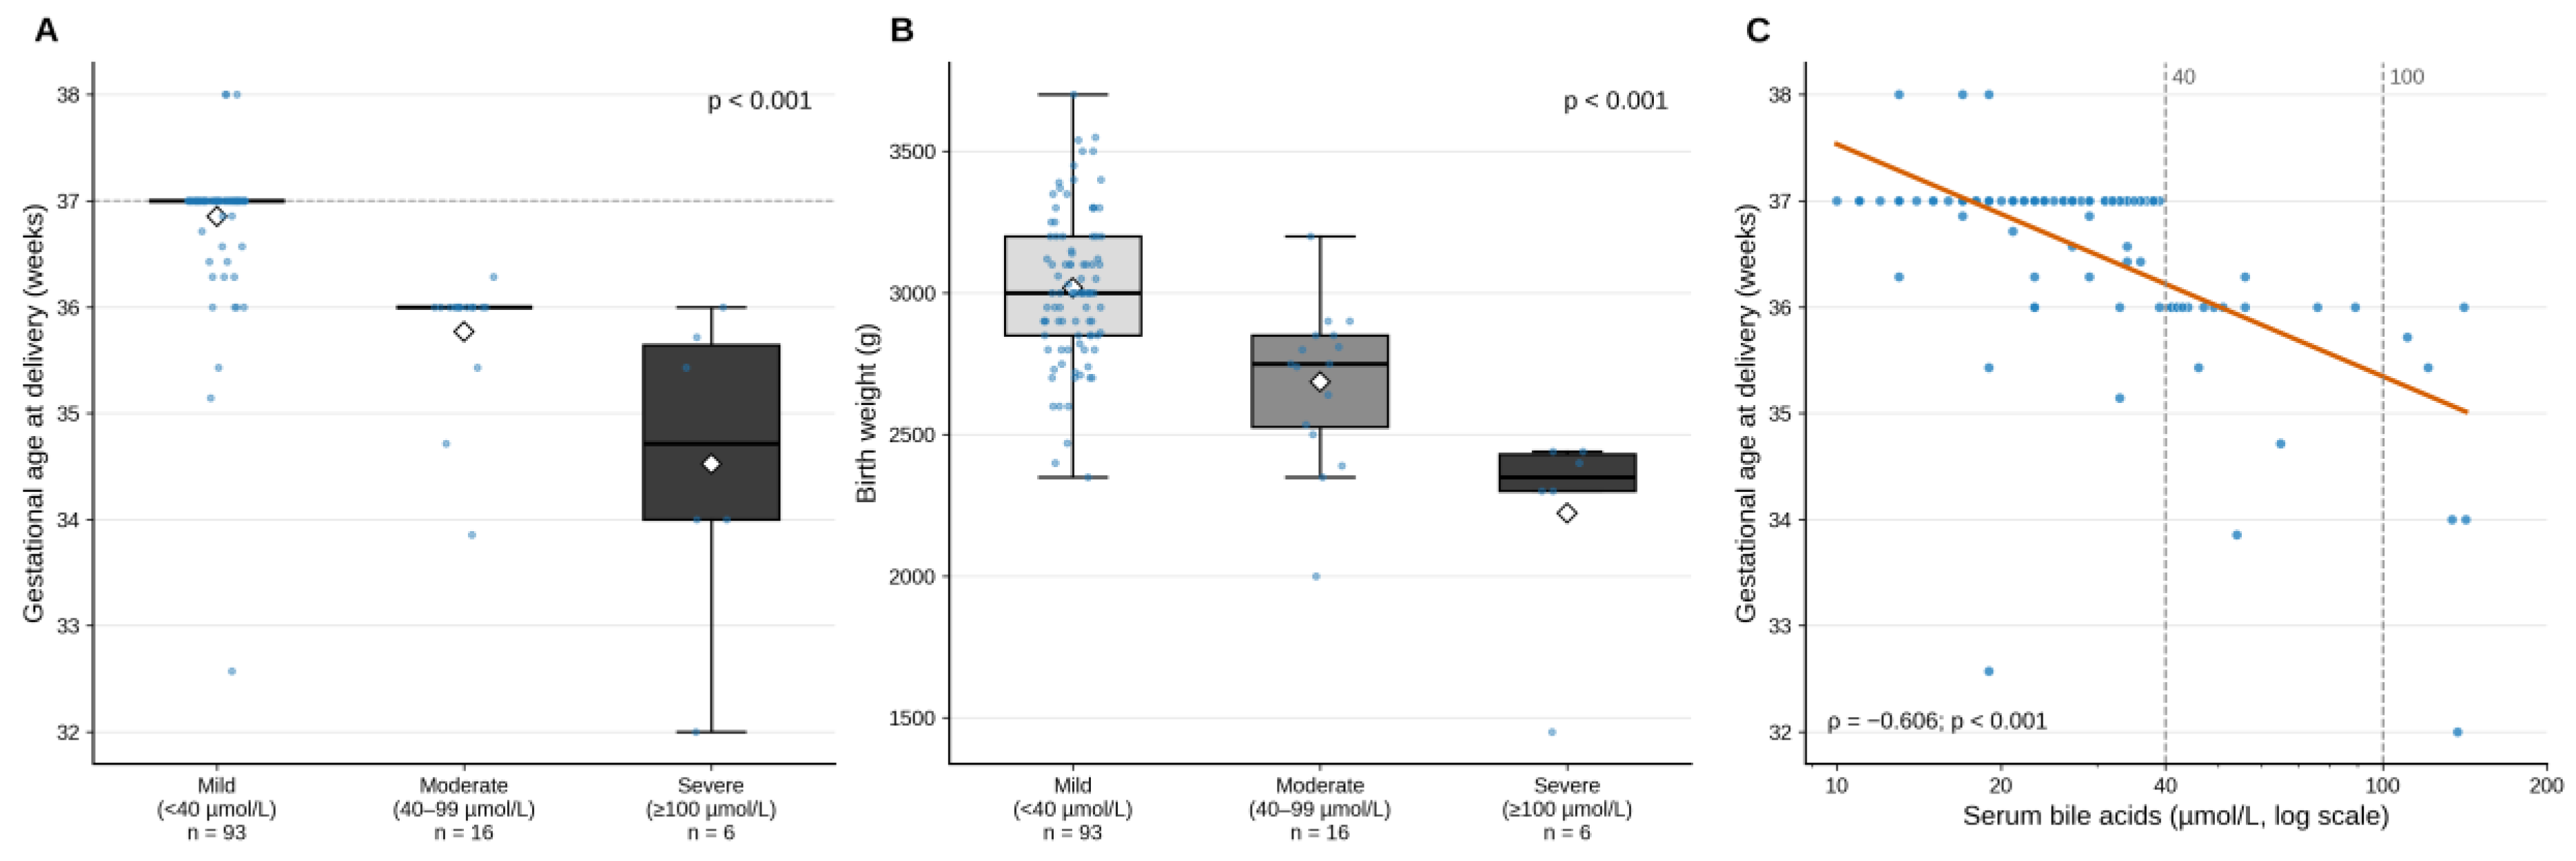
In contrast, perinatal outcomes showed a strong, graded association with severity. Gestational age at delivery declined significantly from mild to severe disease (36.9 ± 0.6, 35.8 ± 0.6 and 34.5 ± 1.5 weeks; p < 0.001), with all pairwise comparisons significant. Birth weight followed a similar pattern (3016.9 ± 262.0, 2685.3 ± 280.4 and 2221.7 ± 383.4 g; p < 0.001), and the difference persisted after adjustment for gestational age at delivery (−194 g for moderate, p = 0.018, and −499 g for severe disease, p < 0.001, relative to mild disease). The 1-minute Apgar score also decreased with increasing severity (7.7 ± 0.5, 7.1 ± 0.7 and 7.0 ± 0.9; p = 0.002), and the proportion with an Apgar score <7 rose from 0% in the mild group to 18.8% and 33.3% in the moderate and severe groups, respectively (p < 0.001). The preterm birth rate was 18.3% in the mild group and 100% in both the moderate and severe groups (p < 0.001). Rates of meconium-stained amniotic fluid (7.5%, 31.3% and 66.7%), fetal distress (5.4%, 43.8% and 66.7%), NICU admission (14.0%, 62.5% and 66.7%) and the composite adverse outcome (32.3%, 100% and 100%) all increased significantly with severity (all p < 0.001) (Table 3, Panels B–C; Figure 4A–B).
Table 3.
(continued). Disease severity groups according to serum bile acids.
| Variable | Mild (<40 µmol/L) n = 93 | Moderate (40–99 µmol/L) n = 16 | Severe (≥100 µmol/L) n = 6 | p |
|---|---|---|---|---|
| B. Disease severity groups by serum bile acids — continuous variables (mean ± SD) | ||||
| Bile acids (µmol/L) | 23.5 ± 8.0 | 52.6 ± 13.7 | 131.0 ± 12.4 | <0.001 |
| AST (U/L) | 26.1 ± 10.1 | 31.3 ± 8.8 | 32.7 ± 18.1 | 0.072 |
| ALT (U/L) | 35.4 ± 24.7 | 40.1 ± 19.8 | 69.2 ± 38.1 | 0.024 |
| Platelets (×10⁹/L) | 230.5 ± 48.7 | 230.4 ± 47.3 | 221.0 ± 24.2 | 0.872 |
| NLR | 3.29 ± 0.87 | 3.32 ± 0.53 | 3.15 ± 0.33 | 0.816 |
| SII (×10⁹/L) | 736.1 ± 158.5 | 750.5 ± 113.2 | 690.1 ± 45.3 | 0.349 |
| APRI | 0.295 ± 0.129 | 0.352 ± 0.116 | 0.375 ± 0.205 | 0.083 |
| FIB-4 | 0.63 ± 0.24 | 0.74 ± 0.24 | 0.49 ± 0.19 | 0.054 |
| Gestational age at delivery (weeks) | 36.9 ± 0.6 | 35.8 ± 0.6 | 34.5 ± 1.5 | <0.001 |
| Birth weight (g) | 3016.9 ± 262.0 | 2685.3 ± 280.4 | 2221.7 ± 383.4 | <0.001 |
| 1-minute Apgar score | 7.7 ± 0.5 | 7.1 ± 0.7 | 7.0 ± 0.9 | 0.002 |
| C. Perinatal outcomes by disease severity, n (%) | ||||
| Preterm birth, n (%) | 17 (18.3) | 16 (100.0) | 6 (100.0) | <0.001 |
| Meconium-stained amniotic fluid, n (%) | 7 (7.5) | 5 (31.3) | 4 (66.7) | <0.001 |
| Fetal distress, n (%) | 5 (5.4) | 7 (43.8) | 4 (66.7) | <0.001 |
| NICU admission, n (%) | 13 (14.0) | 10 (62.5) | 4 (66.7) | <0.001 |
| 1-minute Apgar score <7, n (%) | 0 (0.0) | 3 (18.8) | 2 (33.3) | <0.001 |
| Composite adverse outcome, n (%) | 30 (32.3) | 16 (100.0) | 6 (100.0) | <0.001 |
Panel A: in each cell, the upper line shows mean ± standard deviation and the lower line median (interquartile range); comparisons were performed with the Mann–Whitney U test, or with Welch’s t test for variables normally distributed in both subgroups (age, platelet count and SII). Panel B: Kruskal–Wallis test with Bonferroni correction for pairwise comparisons. Panel C: chi-square / Fisher–Freeman–Halton test. BMI: body mass index; NICU: neonatal intensive care unit.
3.8. Correlations of Bile Acids with Indices and Perinatal Outcomes
On Spearman correlation analysis, serum bile acids were not significantly correlated with any inflammatory or fibrosis index: NLR (ρ = −0.046; p = 0.622), SII (ρ = −0.093; p = 0.321), APRI (ρ = 0.071; p = 0.451), FIB-4 (ρ = 0.002; p = 0.981) and PLR (ρ = 0.069; p = 0.461). The correlation with ALT was of borderline significance (ρ = 0.179; p = 0.056). In contrast, bile acids were significantly and negatively correlated with gestational age at delivery (ρ = −0.606; p < 0.001), birth weight (ρ = −0.467; p < 0.001) and 1-minute Apgar score (ρ = −0.259; p = 0.005) (Figure 4C). Among the indices, the expected moderate correlations were observed between APRI and FIB-4 (ρ = 0.536) and between SII and NLR (ρ = 0.496).
3.9. ROC Analysis for the Prediction of Adverse Perinatal Outcome
Within the ICP group, only serum bile acids showed significant discrimination for the composite adverse perinatal outcome (AUC 0.754; 95% CI 0.659–0.844; p < 0.001). At the Youden-derived cut-off of ≥39 µmol/L, sensitivity was 44.2%, specificity 98.4%, PPV 95.8% and NPV 68.1%. None of the inflammatory or fibrosis indices provided significant prediction: SII (AUC 0.588; p = 0.104), FIB-4 (AUC 0.565; p = 0.222), PLR (AUC 0.543; p = 0.425), NLR (AUC 0.536; p = 0.504) and APRI (AUC 0.466; p = 0.530) (Table 4, Panel B; Figure 2B).
When preterm birth, the most frequent component of the composite outcome, was modelled separately, the predictive performance of bile acids was even more pronounced (AUC 0.843; 95% CI 0.760–0.918; p < 0.001; ≥39 µmol/L: sensitivity 59.0%, specificity 98.7%). In this analysis, SII showed limited but significant discrimination in the unexpected direction, favouring lower values (AUC 0.646; p = 0.005). For NICU admission, only bile acids were significant (AUC 0.678; 95% CI 0.542–0.807; p = 0.009) (Table 4, Panels C–D).
Of the 39 preterm births in the ICP group, 36 (92.3%) were late preterm (34+0 to 36+6 weeks) and only three occurred before 34 weeks; 16 of the 17 preterm births in the mild group occurred after 35 weeks. To examine the influence of protocol-driven timing of delivery, the second composite outcome excluding the preterm component (n = 32; 27.8%) was analysed: bile acids retained significant but more limited discrimination (AUC 0.681; 95% CI 0.558–0.800; p = 0.003; ≥41 µmol/L: sensitivity 46.9%, specificity 91.6%) and remained independent after adjustment for age, BMI, APRI and SII (OR 1.43 per 10 µmol/L; 95% CI 1.17–1.76; p = 0.001). Again, none of the inflammatory or fibrosis indices showed significant discrimination (AUC 0.517 for SII, 0.470 for NLR, 0.523 for PLR and 0.482 for FIB-4; all p > 0.10), whereas APRI showed a borderline inverse association (AUC 0.405; adjusted OR 0.65; p = 0.048). In contrast, among the 76 women who delivered at or after 37 weeks, all of whom had bile acids <40 µmol/L, bile acids did not predict this second composite outcome (AUC 0.49; p = 0.912).
Table 4.
ROC analyses: diagnostic performance of markers for ICP and for the prediction of adverse perinatal outcomes.
Table 4.
ROC analyses: diagnostic performance of markers for ICP and for the prediction of adverse perinatal outcomes.
| Marker | AUC (95% CI) | p | Cut-off | Sensitivity (%) | Specificity (%) | PPV (%) | NPV (%) |
|---|---|---|---|---|---|---|---|
| A. Discrimination of ICP from controls (n = 179) | |||||||
| ALT | 0.895 (0.844–0.940) | <0.001 | ≥20.0 | 75.7 | 96.9 | 97.8 | 68.9 |
| APRI | 0.786 (0.718–0.851) | <0.001 | ≥0.245 | 67.0 | 79.7 | 85.6 | 57.3 |
| AST | 0.782 (0.711–0.843) | <0.001 | ≥21.0 | 72.2 | 68.8 | 80.6 | 57.9 |
| AST/ALT ratio | 0.787 (0.714–0.854) | <0.001 | ≤0.977 | 75.7 | 73.4 | 83.7 | 62.7 |
| NLR | 0.642 (0.555–0.726) | 0.001 | ≥3.189 | 55.7 | 75.0 | 80.0 | 48.5 |
| SII | 0.615 (0.534–0.696) | 0.005 | ≥713.8 | 65.2 | 71.9 | 80.6 | 53.5 |
| FIB-4 | 0.573 (0.481–0.664) | 0.115 | ≥0.546 | 66.1 | 57.8 | 73.8 | 48.7 |
| PLR | 0.466 (0.381–0.551) | 0.435 | ≥118.4 | 47.8 | 67.2 | 72.4 | 41.7 |
| B. Composite adverse perinatal outcome in women with ICP (n = 115) | |||||||
| Bile acids | 0.754 (0.659–0.844) | <0.001 | ≥39.0 | 44.2 | 98.4 | 95.8 | 68.1 |
| SII (low values) | 0.588 (0.481–0.693) | 0.104 | ≤747.3 | 59.6 | 58.7 | 54.4 | 63.8 |
| FIB-4 | 0.565 (0.458–0.667) | 0.222 | ≥0.677 | 40.4 | 74.6 | 56.8 | 60.3 |
| PLR | 0.543 (0.439–0.649) | 0.425 | ≥106.8 | 67.3 | 54.0 | 54.7 | 66.7 |
| NLR (low values) | 0.536 (0.428–0.643) | 0.504 | ≤4.018 | 94.2 | 20.6 | 49.5 | 81.2 |
| APRI | 0.466 (0.356–0.573) | 0.530 | ≥0.457 | 13.5 | 93.7 | 63.6 | 56.7 |
| C. Preterm birth (<37 weeks) in women with ICP (n = 115) | |||||||
| Bile acids | 0.843 (0.760–0.918) | <0.001 | ≥39.0 | 59.0 | 98.7 | 95.8 | 82.4 |
| SII (low values) | 0.646 (0.542–0.747) | 0.005 | ≤747.3 | 69.2 | 60.5 | 47.4 | 79.3 |
| FIB-4 | 0.578 (0.458–0.692) | 0.189 | ≥0.703 | 43.6 | 77.6 | 50.0 | 72.8 |
| APRI | 0.552 (0.440–0.663) | 0.363 | ≥0.457 | 17.9 | 94.7 | 63.6 | 69.2 |
| D. NICU admission in women with ICP (n = 115) | |||||||
| Bile acids | 0.678 (0.542–0.807) | 0.009 | ≥41.0 | 51.9 | 90.9 | 63.6 | 86.0 |
| SII | 0.481 (0.358–0.607) | 0.762 | ≥646.7 | 81.5 | 27.3 | 25.6 | 82.8 |
| FIB-4 | 0.520 (0.406–0.638) | 0.744 | ≥0.532 | 81.5 | 36.4 | 28.2 | 86.5 |
| APRI | 0.429 (0.314–0.551) | 0.242 | ≥0.271 | 63.0 | 45.5 | 26.2 | 80.0 |
AUC: area under the curve; PPV: positive predictive value; NPV: negative predictive value; NICU: neonatal intensive care unit. Cut-off values were determined by the Youden index, and 95% confidence intervals were computed with 4000 bootstrap replicates. “Low values” indicates that lower levels of the marker were associated with the event. AUC comparisons (DeLong test): ALT vs. APRI p = 0.003; APRI vs. AST/ALT ratio p = 0.993; APRI vs. SII p = 0.004; APRI vs. NLR p = 0.001. PPV and NPV were calculated for the proportion of ICP in the sample (64.2%); at a population prevalence of 1%, the PPV and NPV of APRI ≥0.245 are 3.2% and 99.6%, respectively.
3.10. Multivariable Logistic Regression Analyses
To identify independent predictors of ICP, a logistic regression model including age, BMI, APRI and SII was fitted (n = 179). Each 0.1-unit increase in APRI increased the odds of ICP 3.36-fold (95% CI 2.16–5.25; p < 0.001), and each 100-unit increase in SII 1.45-fold (95% CI 1.08–1.96; p = 0.014). BMI showed an independent inverse association (OR 0.88; 95% CI 0.78–0.99; p = 0.027), whereas age was not significant (p = 0.089). The model was significant overall (p < 0.001; Nagelkerke R² = 0.380), with no evidence of multicollinearity (all VIF ≤ 1.08). In a sensitivity analysis additionally including NLR (all VIF ≤ 1.55), APRI (OR 4.32) and SII (OR 1.71) remained independent, whereas NLR, which was positively associated with ICP in univariable analysis, reversed direction (OR 0.76; p = 0.064); this sign reversal was interpreted as a suppression effect arising from the mathematical inclusion of NLR within SII (Table 5, Panel A).
In the prespecified model for the composite adverse perinatal outcome in the ICP group (bile acids, APRI, SII, age and BMI), bile acids remained the only independent predictor: OR 2.39 per 10 µmol/L increase (95% CI 1.54–3.69; p < 0.001). SII (OR 0.78; p = 0.092), APRI (OR 0.81; p = 0.239), age (p = 0.122) and BMI (p = 0.981) did not contribute significantly (Nagelkerke R² = 0.384; all VIF ≤ 1.07) (Table 5, Panel B). The result was unchanged in an alternative model including all variables with p < 0.20 in univariable analysis (bile acids, age, FIB-4, SII and NLR) together with BMI: the OR for bile acids was 2.30 (95% CI 1.49–3.56; p < 0.001), and no other variable was significant (FIB-4 p = 0.107; SII p = 0.956; NLR p = 0.181; Nagelkerke R² = 0.398; all VIF ≤ 2.34). In the model for preterm birth including age and BMI, each 10 µmol/L increase in bile acids increased the risk 3.89-fold (95% CI 2.18–6.91; p < 0.001), whereas each 100-unit increase in SII showed an inverse association (OR 0.64; 95% CI 0.45–0.91; p = 0.014) (Nagelkerke R² = 0.551; Table 5, Panel C).
Table 5.
Logistic regression analyses.
| Variable | Univariable OR (95% CI) | p | Multivariable OR (95% CI) | p |
|---|---|---|---|---|
| A. Predictors of ICP (n = 179; model p < 0.001; Nagelkerke R² = 0.380) | ||||
| Age (years) | 1.034 (0.975–1.097) | 0.265 | 1.063 (0.991–1.141) | 0.089 |
| BMI (kg/m²) | 0.882 (0.801–0.972) | 0.011 | 0.875 (0.778–0.985) | 0.027 |
| APRI (per 0.1-unit increase) | 3.200 (2.106–4.862) | <0.001 | 3.364 (2.156–5.248) | <0.001 |
| SII (per 100-unit increase) | 1.237 (0.976–1.569) | 0.079 | 1.455 (1.079–1.961) | 0.014 |
| NLR (per 0.5-unit increase) | 1.290 (1.053–1.579) | 0.014 | — | — |
| B. Predictors of the composite adverse perinatal outcome in the ICP group (n = 115; model p < 0.001; Nagelkerke R² = 0.384) | ||||
| Bile acids (per 10 µmol/L increase) | 2.292 (1.516–3.465) | <0.001 | 2.385 (1.539–3.694) | <0.001 |
| APRI (per 0.1-unit increase) | 0.959 (0.726–1.267) | 0.767 | 0.808 (0.568–1.151) | 0.239 |
| FIB-4 (per 0.1-unit increase) | 1.147 (0.975–1.350) | 0.097 | — | — |
| SII (per 100-unit increase) | 0.809 (0.627–1.044) | 0.103 | 0.775 (0.576–1.043) | 0.092 |
| NLR (per 0.5-unit increase) | 0.853 (0.673–1.080) | 0.187 | — | — |
| Age (years) | 1.064 (0.990–1.143) | 0.092 | 1.068 (0.983–1.161) | 0.122 |
| BMI (kg/m²) | 1.004 (0.893–1.130) | 0.941 | 0.998 (0.865–1.153) | 0.981 |
| C. Predictors of preterm birth in the ICP group (n = 115; model p < 0.001; Nagelkerke R² = 0.551) | ||||
| Bile acids (per 10 µmol/L increase) | 3.529 (2.079–5.990) | <0.001 | 3.885 (2.184–6.912) | <0.001 |
| SII (per 100-unit increase) | 0.746 (0.571–0.976) | 0.032 | 0.639 (0.446–0.913) | 0.014 |
| APRI (per 0.1-unit increase) | 1.203 (0.901–1.607) | 0.210 | 1.005 (0.668–1.510) | 0.982 |
| BMI (kg/m²) | 1.010 (0.893–1.143) | 0.872 | 1.031 (0.870–1.221) | 0.728 |
| Age (years) | 1.019 (0.947–1.096) | 0.617 | 1.005 (0.913–1.107) | 0.912 |
| D. Effect of ICP on perinatal outcomes: crude and BMI- and age-adjusted odds ratios (n = 179) | ||||
| Preterm birth (<37 weeks) | 2.77 (1.27–6.03) | 0.010 | 2.71 (1.23–6.00) | 0.014 |
| Meconium-stained amniotic fluid | 2.42 (0.77–7.59) | 0.128 | 2.26 (0.70–7.22) | 0.171 |
| Fetal distress | 1.32 (0.51–3.39) | 0.569 | 1.15 (0.43–3.04) | 0.781 |
| NICU admission | 1.00 (0.49–2.06) | 0.995 | 0.93 (0.44–1.96) | 0.856 |
| Composite adverse perinatal outcome | 1.69 (0.89–3.20) | 0.107 | 1.56 (0.81–3.01) | 0.182 |
OR: odds ratio; CI: confidence interval; BMI: body mass index; VIF: variance inflation factor. Panel A multivariable model: age, BMI, APRI and SII (all VIF ≤ 1.08); NLR was not entered into the main model because it is a component of SII — in the sensitivity model including NLR, the OR was 4.33 for APRI, 1.71 for SII and 0.76 for NLR (p = 0.064). Panel B multivariable model: bile acids, SII, APRI, age and BMI (all VIF ≤ 1.07); variables analysed univariably but not entered into the model are shown as “—”. Panel C model: bile acids, SII, APRI, age and BMI. Panel D: in each row, the dependent variable is the respective perinatal outcome and the independent variable is group (ICP / control); adjusted models include BMI and age simultaneously — in this panel, the “univariable” column shows crude and the “multivariable” column adjusted odds ratios.
4. Discussion
In this study, we showed that routine laboratory data obtained as early as 11–14 weeks of gestation in women who subsequently developed ICP carried a measurable hepatocellular and inflammatory signature months before the disease became clinically apparent. First-trimester APRI was approximately 60% higher in the ICP group than in controls, with a large effect size (Cohen’s d = 1.01), and SII and NLR also differed significantly, albeit with small-to-moderate effect sizes. In multivariable analysis, APRI and SII remained independent predictors of ICP after adjustment for age and BMI; however, this signal largely reflected transaminase elevation and added no meaningful discrimination beyond that provided by ALT alone. The second, and clinically decisive, finding of the study is negative: none of these indices predicted the adverse perinatal outcome, preterm birth or NICU admission among women with ICP; they were unrelated to disease severity and uncorrelated with serum bile acids. As expected, the only variable determining perinatal risk was serum bile acid concentration.
Our findings regarding the inflammatory indices are consistent with the scattered and partly conflicting literature. In a retrospective study at Ankara Etlik City Hospital comparing 121 women with ICP and 121 controls, Özkan et al. found SII and NLR to be significantly higher in ICP, but the AUC for SII was only 0.581 (10); this value is almost identical to the 0.615 we obtained from first-trimester rather than third-trimester measurements. Ergani and Celen, following 218 pregnant women from the first trimester to delivery to examine the course of SII across all three trimesters, reported that the difference became evident in second-trimester SII and that this value was particularly high in severe ICP (92% sensitivity and 96% specificity for second-trimester SII) (11); the small effect size we observed in the first trimester is consistent with this observation. Çallıoğlu et al., comparing 173 women with ICP and 266 controls, suggested that elevated SII supports the inflammatory nature of ICP but does not contribute to diagnosis or severity assessment, whereas PLR may be useful (12). In contrast, in a recent study by Kurt and Yılmaz of 186 cases and 244 controls with indices calculated at diagnosis, the aggregate index of systemic inflammation (AISI), NLR, SII and SIRI did not differ between groups, while neutrophil and lymphocyte counts were lower and PLR higher in ICP (13). This contradictory result illustrates how markedly the behaviour of haemogram-based indices in ICP varies between studies. Ji et al., comparing 113 women with ICP and 209 controls, reported NLR as an independent factor for ICP (OR 1.885) that was higher in severe than in mild disease (14); in our series, NLR did not differ across severity groups (p = 0.816), a discrepancy that may be explained by our measurements having been obtained before the disease developed.
Earlier studies show a similar heterogeneity. In the series of Yayla Abide et al. comparing 84 women with ICP and 145 healthy pregnant women, NLR did not differ between groups, whereas leucocyte count, mean platelet volume (MPV) and PLR were higher and RDW lower, with MPV being the only marker associated with severity (15). In their small series of 33 cases and 33 controls, Silva et al. found no difference in any complete blood count parameter in the first trimester, with differences emerging only in the third trimester and, moreover, in the unexpected direction (lower leucocyte and neutrophil counts and NLR) (16). The study by Shen et al., which compared 49 women with ICP with 250 healthy pregnant women at disease onset and with 1439 in early pregnancy, has the design closest to ours and directly supports our findings: the authors reported that, in early pregnancy before disease onset, platelet parameters such as plateletcrit and PDW, as well as neutrophil count, NLR, SIRI and SII, were significantly higher in women who later developed ICP, and that SII was an independent risk factor for the development of ICP (17). In the study by Ozgen et al. of 80 cases and 120 controls, NLR and platelet count were higher and RDW lower, but the strongest discrimination was provided by fibrinogen, a coagulation parameter rather than an inflammatory marker (18). Taken together, these heterogeneous results suggest that haemogram-based indices reflect a real but small inflammatory signal in ICP that lacks the discriminative power required for individual diagnostic decisions. The AUCs of 0.61–0.64 obtained for SII and NLR in our data support precisely this interpretation.
Our findings on the fibrosis indices rest on a more consistent body of literature. Obut et al., comparing 80 women with ICP and 200 controls and measuring markers both in the first trimester and at diagnosis, showed that ALBI, MELD and APRI scores were significantly higher in ICP at both time points and remained independent in multivariable analysis (19). This result provides independent confirmation of our first-trimester APRI finding. In a prospective study of 71 women with ICP and 71 controls, Cemortan et al. reported both APRI and FIB-4 as reliable markers associated with major complications of the disease (20). Eyisoy et al. reported that, in 101 women with ICP, APRI calculated at diagnosis distinguished severe from mild disease with 82% sensitivity and 72% specificity at a cut-off of 1.06, was moderately correlated with fasting bile acids (r = 0.445) and was associated with meconium-stained amniotic fluid, NICU admission and preterm birth (21). In the retrospective study by Cicek et al. of 105 women with ICP and 112 controls, APRI calculated at diagnosis discriminated ICP with an AUC of 0.902, and FIB-4 also showed a smaller but significant difference (22). The finding that APRI performed best among the derived markers in our series (AUC 0.786) is consistent with these studies; our lower AUC compared with the 0.902 reported at diagnosis may be explained by the first-trimester timing of our measurements. The cut-off of 1.06 reported by Eyisoy et al. and our value of 0.245 are not directly comparable: the former aims to discriminate severity among women with ICP in the third trimester, whereas the latter aims to distinguish ICP that is not yet clinically apparent from healthy pregnancy in the first trimester. Moreover, the association between APRI at diagnosis and bile acids and perinatal outcomes reported by Eyisoy et al. was not observed in our series, a difference consistent with the interpretation that first-trimester APRI reflects early hepatocellular susceptibility rather than disease severity.
The absence of significant findings for FIB-4 in any analysis is not unexpected and stems from the structure of the formula. FIB-4 contains the square root of ALT in its denominator and age in its numerator (9). Hepatocellular injury in ICP is ALT-predominant, as reflected in the significantly lower AST/ALT ratio in our ICP group (0.87 vs. 1.34; p < 0.001); the rise in ALT therefore mathematically dampens the contribution of the rise in AST to the index. In addition, the discriminative power of this score, developed in populations with chronic liver disease, depends largely on age, a component that remains nearly constant in a young pregnant population with a narrow age range such as ours. The absence of ALT from the APRI denominator, and its reliance on the direct AST/platelet relationship, explains why it discriminates much better in the same population.
Two points should be emphasised in interpreting the diagnostic findings. First, first-trimester ALT alone discriminated ICP better than any derived index (AUC 0.895), and adding APRI and SII to ALT did not significantly improve discrimination. The finding that ALT exceeded 40 U/L in the first trimester in more than one third of women with ICP suggests that, in some of these women, ICP may be associated with a subclinical hepatocellular process beginning well before clinical manifestations, but also that coexisting conditions such as undiagnosed fatty liver disease may have contributed. The diagnostic value of APRI thus derives largely from its AST component, with only a limited contribution from the haemogram component. Second, selecting controls with normal liver tests may have artificially inflated the discrimination of transaminase-based markers (spectrum bias). Furthermore, in a case–control design, PPV and NPV depend on the proportion of cases in the sample; the PPV of 85.6% falls to 3.2% at a population prevalence of 1%. The use of first-trimester APRI for screening is therefore not supported by the present data.
The most important negative finding of the study is that first-trimester indices did not predict perinatal outcome. This is not surprising from a pathophysiological standpoint: fetal harm in ICP results from the direct effects of bile acids crossing the placenta on fetal cardiomyocytes and the myometrium rather than from the maternal inflammatory burden (2). In the aggregate data meta-analysis of 5557 cases from 23 studies and the individual patient data meta-analysis of 5269 cases from 27 studies by Ovadia et al., the stillbirth rate in singleton pregnancies increased from 0.13% in women with bile acids <40 µmol/L to 3.44% in those with ≥100 µmol/L, with a significant increase in risk demonstrated only in the latter group (3). The meta-analysis by Cui et al. reported a graded relationship between increasing bile acid concentrations and the risks of preterm birth, meconium-stained amniotic fluid and NICU admission (23). Çelik et al. found that preterm birth and NICU admission increased above a cut-off of approximately 34 µmol/L in 370 women with ICP (24), and Marschall’s review emphasised that fetal risk becomes evident above 40 µmol/L (25). In our series, however, the Youden-derived cut-off of ≥39 µmol/L and its specificity of 98.4% must be interpreted with caution: because women with bile acids ≥40 µmol/L were delivered before 37 weeks according to institutional protocol, the 100% rates of preterm birth, and hence of the composite outcome, in the moderate and severe groups are largely definitional, and the cut-off essentially reproduces the protocol threshold. Because of this circularity, in our sensitivity analysis excluding the preterm component, bile acids continued to predict the composite of meconium, fetal distress, NICU admission and low Apgar score, but with markedly reduced discrimination (AUC from 0.754 to 0.681); moreover, no such association was observed among women delivered at 37 weeks with bile acids <40 µmol/L. These findings indicate that the association between bile acids and perinatal risk is genuine, but that its magnitude in our series was inflated by bile acid–based decisions on the timing of delivery. The sensitivity of only 44.2% also suggests that a low bile acid concentration does not in itself provide reassurance. The graded deterioration across severity subgroups — the decline in gestational age at delivery from 36.9 to 34.5 weeks and preterm birth rates of 100% in the moderate and severe groups — is consistent with guideline recommendations for severity-based surveillance and timing of delivery (4,8,26). The persistence of the severity-related reduction in birth weight after adjustment for gestational age suggests a fetal effect beyond earlier delivery in severe disease, but with only six women in the severe group this observation remains hypothesis-generating.
The inverse association of SII with preterm birth, favouring lower values (AUC 0.646; multivariable OR 0.64; p = 0.014), should be interpreted with caution and is most probably not causal. Most preterm births in our series were late preterm, and a substantial proportion appear to have been related to decisions to deliver early because of high bile acid concentrations; moreover, because SII was measured in the first trimester, months before delivery, it was not affected by labour-related neutrophilia. The absence of a significant correlation between bile acids and SII (ρ = −0.093; p = 0.321) further suggests that the two pathways operate independently. We therefore interpret this finding not as a protective effect of low SII but as a chance distributional difference within the group of iatrogenic preterm births driven by high bile acids — a hypothesis-generating observation that requires confirmation.
From a therapeutic perspective, our findings support the current approach whereby surveillance remains centred on bile acids. The individual participant data meta-analysis by Ovadia et al. showed that ursodeoxycholic acid confers only limited benefit on perinatal outcomes, particularly when used alone and in mild disease (27), and the PITCHES trial by Chappell et al., which randomised 605 women, found no difference in the composite perinatal outcome between ursodeoxycholic acid and placebo (28). The Cochrane review by Walker et al. likewise concluded that the evidence on the effect of current pharmacological interventions on perinatal outcomes is insufficient (29). In the absence of an effective pharmacological option, risk stratification and timing of delivery remain the mainstay of clinical management; this makes the search for a marker that could replace bile acid measurement all the more relevant, but our data indicate that haemogram-based indices cannot fill this gap.
The limited predictive power of first-trimester indices is consistent with their performance in other obstetric applications. Cevher Akdulum et al. examined the association of first-trimester SII with pre-eclampsia in 130 pregnant women and obtained only moderate predictive performance (30). Karataş et al., investigating the value of AISI, NLR, SII and SIRI calculated at 11–14 weeks for predicting gestational diabetes and related obstetric outcomes, similarly reported limited discrimination (31). These two studies show that first-trimester haemogram indices are generally significant at the group level but insufficient at the individual level for pregnancy complications, and our results confirm this pattern for ICP. It should also be borne in mind that coexisting metabolic disease increases risk: in the multicentre cohort of 2178 women with ICP reported by Li et al., coexisting gestational diabetes significantly aggravated adverse perinatal outcomes (32).
The higher BMI in the control group and its independent inverse association with ICP in the multivariable model (OR 0.88; p = 0.027) should be regarded as a design-related finding rather than a biological protective effect. The selection of controls from women followed at the same centre and the mean BMI above 29 kg/m² in both groups point to a high weight profile across the whole population, in which a difference of 1.3 kg/m² is of limited clinical relevance. Indeed, BMI was not an independent predictor in any model of perinatal outcome (all p > 0.15), and all effect sizes remained practically unchanged after adjustment for BMI and age, indicating that the main findings are robust to confounding.
Strengths and Limitations
The main strength of this study is that the indices were evaluated before disease onset, in the first trimester; most previous studies performed measurements at diagnosis, thereby blurring the distinction between prediction and diagnosis. Additional methodological strengths include the evaluation of both the diagnostic and the predictive question in the same cohort, the three-category bile acid–based severity subgroup analysis, adjustment for BMI and age in all models, bootstrap estimation of AUC confidence intervals and the reporting of effect sizes.
Several limitations should be acknowledged. First, the study was single-centre and retrospective, so incomplete record-based information and selection bias cannot be fully excluded. Second, selecting controls with normal liver tests may have introduced spectrum bias, exaggerating the discrimination of transaminase-based markers (ALT, AST and APRI); owing to the imbalance between case and control numbers (115 vs. 64) and the case–control design, PPV and NPV cannot be generalised to the population level. Third, the predictive analyses within the ICP group were adequately powered for effects of AUC 0.65 but had limited power for smaller effects; the finding that the indices did not predict perinatal outcome therefore does not exclude a small association. The limitation of the severe subgroup to six women also means that the proportions in this group carry wide uncertainty. Fourth, the composite outcome weights components of differing clinical importance (such as NICU admission and fetal distress) equally. Fifth, and perhaps most importantly, because delivery was planned at 37 weeks in women with ICP, and earlier when bile acids were ≥40 µmol/L, according to institutional protocol, and because the mode of labour onset was not recorded, preterm births could not be classified as spontaneous or iatrogenic; part of the strong association between bile acids and preterm birth therefore stems from the clinical decision-making process. Sixth, a threshold of ≥10 µmol/L was used for the diagnosis of ICP; had the ≥19 µmol/L threshold recommended by the Royal College of Obstetricians and Gynaecologists (33) been applied, 26 women (22.6%) would not have met the diagnostic criterion. Seventh, although first-trimester ALT exceeded 40 U/L in 35.7% of women with ICP, imaging data for hepatic steatosis and comprehensive hepatitis serology could not be included in the analyses; a contribution of coexisting subclinical liver disease therefore cannot be excluded. Eighth, the dose, timing of initiation and response to ursodeoxycholic acid, as well as neonatal sex, were not available in the records and could not be analysed, and birth weight could not be expressed as a percentile. Finally, no stillbirths occurred in our series; our findings therefore cannot be generalised to the most severe outcome of ICP. Multicentre prospective cohorts with serial measurement of the indices throughout pregnancy and detailed recording of delivery timing are needed to address these questions.
5. Conclusions
The APRI score calculated from routine haemogram and liver tests obtained at 11–14 weeks of gestation is significantly elevated months before clinical presentation in women who subsequently develop ICP and provides the highest diagnostic discrimination among the derived markers (AUC 0.786, comparable to the AST/ALT ratio); SII and NLR show statistically significant but clinically inadequate discrimination, and FIB-4 and PLR contribute nothing. However, these indices do not add meaningfully to the discrimination provided by first-trimester ALT alone. These findings support the view that, in a subset of women, ICP may be associated with a hepatocellular–inflammatory process beginning in early pregnancy.
In contrast, none of the first-trimester indices predicts adverse perinatal outcome, preterm birth or NICU admission, is related to disease severity or correlates with serum bile acids. Serum bile acid concentration is the only independent variable associated with perinatal risk, although the magnitude of this association is influenced by the bile acid–based delivery-timing protocol. First-trimester APRI and SII should therefore remain research-stage early risk markers until validated in prospective studies, and decisions on the intensity of surveillance, frequency of antenatal visits and timing of delivery in ICP should continue to be based on bile acid measurement.
Peer review
Externally peer-reviewed.
Author Contributions
All authors contributed to the concept and design; data collection and processing; analysis and interpretation; literature review; and drafting and critical revision of the manuscript, and all approved the final version for publication.
Funding
This study received no financial support from any institution or organisation.
Institutional Review Board Statement
This single-center, retrospective case–control study was approved by the Non-Interventional Clinical Research Ethics Committee of İzmir City Hospital (date:22.07.2026, decision no. 2026/442), and all procedures were performed in accordance with the principles of the Declaration of Helsinki.
Informed Consent Statement
Because of the retrospective design and the use of anonymized hospital records, the ethics committee waived the requirement for individual informed consent.
Data Availability Statement
The anonymised dataset supporting this study is available from the corresponding author upon reasonable request.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Williamson C, Geenes V. Intrahepatic cholestasis of pregnancy. Obstet Gynecol. 2014;124(1):120-133. [CrossRef]
- Xiao J, Li Z, Song Y, et al. Molecular pathogenesis of intrahepatic cholestasis of pregnancy. Can J Gastroenterol Hepatol. 2021;2021:6679322. [CrossRef]
- Ovadia C, Seed PT, Sklavounos A, et al. Association of adverse perinatal outcomes of intrahepatic cholestasis of pregnancy with biochemical markers: results of aggregate and individual patient data meta-analyses. Lancet. 2019;393(10174):899-909. [CrossRef]
- Lee RH, Greenberg M, Metz TD, Pettker CM; Society for Maternal-Fetal Medicine (SMFM). Society for Maternal-Fetal Medicine Consult Series #53: Intrahepatic cholestasis of pregnancy. Am J Obstet Gynecol. 2021;224(2):B2-B9. [CrossRef]
- Hu B, Yang XR, Xu Y, et al. Systemic immune-inflammation index predicts prognosis of patients after curative resection for hepatocellular carcinoma. Clin Cancer Res. 2014;20(23):6212-6222. [CrossRef]
- Wai CT, Greenson JK, Fontana RJ, et al. A simple noninvasive index can predict both significant fibrosis and cirrhosis in patients with chronic hepatitis C. Hepatology. 2003;38(2):518-526. [CrossRef]
- von Elm E, Altman DG, Egger M, Pocock SJ, Gøtzsche PC, Vandenbroucke JP. The Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement: guidelines for reporting observational studies. Lancet. 2007;370(9596):1453-1457. [CrossRef]
- Hobson SR, Cohen ER, Gandhi S, et al. Guideline No. 452: Diagnosis and management of intrahepatic cholestasis of pregnancy. J Obstet Gynaecol Can. 2024;46(8):102618. [CrossRef]
- Sterling RK, Lissen E, Clumeck N, et al. Development of a simple noninvasive index to predict significant fibrosis in patients with HIV/HCV coinfection. Hepatology. 2006;43(6):1317-1325. [CrossRef]
- Özkan S, Aksan A, Kurt D, et al. Are systemic inflammation markers reliable for diagnosing intrahepatic cholestasis of pregnancy? A retrospective cohort study. Am J Reprod Immunol. 2024;92(4):e13937. [CrossRef]
- Ergani SY, Celen S. Role of systemic immune inflammatory index to predict intrahepatic cholestasis of pregnancy. Clin Lab. 2024;70(3). [CrossRef]
- Çallıoğlu N, Tuna G, Tandoğan Ö, et al. Systemic immune-inflammatory index and platelet-to-lymphocyte ratio in intrahepatic cholestasis of pregnancy. Saudi Med J. 2024;45(11):1217-1222. [CrossRef]
- Kurt D, Yilmaz A. Inflammatory hematologic indices in intrahepatic cholestasis of pregnancy: a retrospective case-control study focusing on the aggregate index of systemic inflammation. BMC Pregnancy Childbirth. 2026;26(1):366. [CrossRef]
- Ji D, Sheng M, Zhang L, et al. Diagnostic value of neutrophil-to-lymphocyte ratio (NLR) in intrahepatic cholestasis of pregnancy. Br J Hosp Med (Lond). 2025;86(1):1-10. [CrossRef]
- Yayla Abide Ç, Vural F, Kılıççı Ç, et al. Can we predict severity of intrahepatic cholestasis of pregnancy using inflammatory markers? Turk J Obstet Gynecol. 2017;14(3):160-165. [CrossRef]
- Silva J, Magenta M, Sisti G. Association between complete blood count components and intrahepatic cholestasis of pregnancy. Cureus. 2020;12(12):e12381. [CrossRef]
- Shen C, Hu W, Wu T, et al. Analysis of changes in platelet parameters and inflammatory markers in intrahepatic cholestasis of pregnancy before disease development. Am J Transl Res. 2024;16(12):7448-7457. [CrossRef]
- Ozgen L, Ozgen G, Karasin SS, et al. Fibrinogen levels and total serum bile acids in intrahepatic cholestasis of pregnancy. J Coll Physicians Surg Pak. 2022;32(11):1404-1409. [CrossRef]
- Obut M, Kından A, Ibanoğlu MC, et al. Liver damage parameters and peripheral blood parameters for prediction and diagnosis of intrahepatic cholestasis in pregnancy. J Obstet Gynaecol Res. 2024;50(2):196-204. [CrossRef]
- Cemortan M, Iliadi-Tulbure C, Sagaidac I, et al. Assessment of aspartate aminotransferase to platelet ratio index and fibrosis-4 index score on women with intrahepatic cholestasis of pregnancy. AJOG Glob Rep. 2024;4(2):100337. [CrossRef]
- Eyisoy ÖG, Taşdemir Ü, Eriç Özdemir M, et al. Aspartate aminotransferase to platelet ratio index (APRI) score: is it useful in patients with intrahepatic cholestasis of pregnancy? J Matern Fetal Neonatal Med. 2022;35(25):10137-10142. [CrossRef]
- Cicek S, Kapudere B, Parspancı YBK, et al. Diagnostic utility of APRI, FIB-4, and FIB-5 in intrahepatic cholestasis of pregnancy: a retrospective case-control study. Int J Gynaecol Obstet. 2026;174(1):253-263. [CrossRef]
- Cui D, Zhong Y, Zhang L, et al. Bile acid levels and risk of adverse perinatal outcomes in intrahepatic cholestasis of pregnancy: a meta-analysis. J Obstet Gynaecol Res. 2017;43(9):1411-1420. [CrossRef]
- Çelik S, Çalışkan CS, Çelik H, et al. Predictors of adverse perinatal outcomes in intrahepatic cholestasis of pregnancy. Ginekol Pol. 2019;90(4):217-222. [CrossRef]
- Marschall HU. Management of intrahepatic cholestasis of pregnancy. Expert Rev Gastroenterol Hepatol. 2015;9(10):1273-1279. [CrossRef]
- Giouleka S, Zafeirati C, Siargkas A, et al. Intrahepatic cholestasis of pregnancy: a comparative review of guidelines. Obstet Gynecol Surv. 2025;80(11):717-730. [CrossRef]
- Ovadia C, Sajous J, Seed PT, et al. Ursodeoxycholic acid in intrahepatic cholestasis of pregnancy: a systematic review and individual participant data meta-analysis. Lancet Gastroenterol Hepatol. 2021;6(7):547-558. [CrossRef]
- Chappell LC, Bell JL, Smith A, et al. Ursodeoxycholic acid versus placebo in women with intrahepatic cholestasis of pregnancy (PITCHES): a randomised controlled trial. Lancet. 2019;394(10201):849-860. [CrossRef]
- Walker KF, Chappell LC, Hague WM, et al. Pharmacological interventions for treating intrahepatic cholestasis of pregnancy. Cochrane Database Syst Rev. 2020;7(7):CD000493. [CrossRef]
- Cevher Akdulum MF, Demirdağ E, Arık Sİ, et al. Is the first-trimester systemic immune-inflammation index associated with preeclampsia? Cureus. 2023;15(8):e44063. [CrossRef]
- Karatas E, Tanacan A, Ozkavak OO, et al. Predictive value of first-trimester aggregate index of systemic inflammation (AISI) and other inflammatory indices for gestational diabetes mellitus and associated obstetric outcomes. Am J Reprod Immunol. 2025;93(4):e70069. [CrossRef]
- Li X, Cai QY, Luo X, et al. Gestational diabetes mellitus aggravates adverse perinatal outcomes in women with intrahepatic cholestasis of pregnancy. Diabetol Metab Syndr. 2024;16(1):57. [CrossRef]
- Girling J, Knight CL, Chappell L; Royal College of Obstetricians and Gynaecologists. Intrahepatic cholestasis of pregnancy: Green-top Guideline No. 43 June 2022. BJOG. 2022;129(13):e95-e114. [CrossRef]
Figure 1.
Flow diagram of participant selection. ICP: intrahepatic cholestasis of pregnancy.
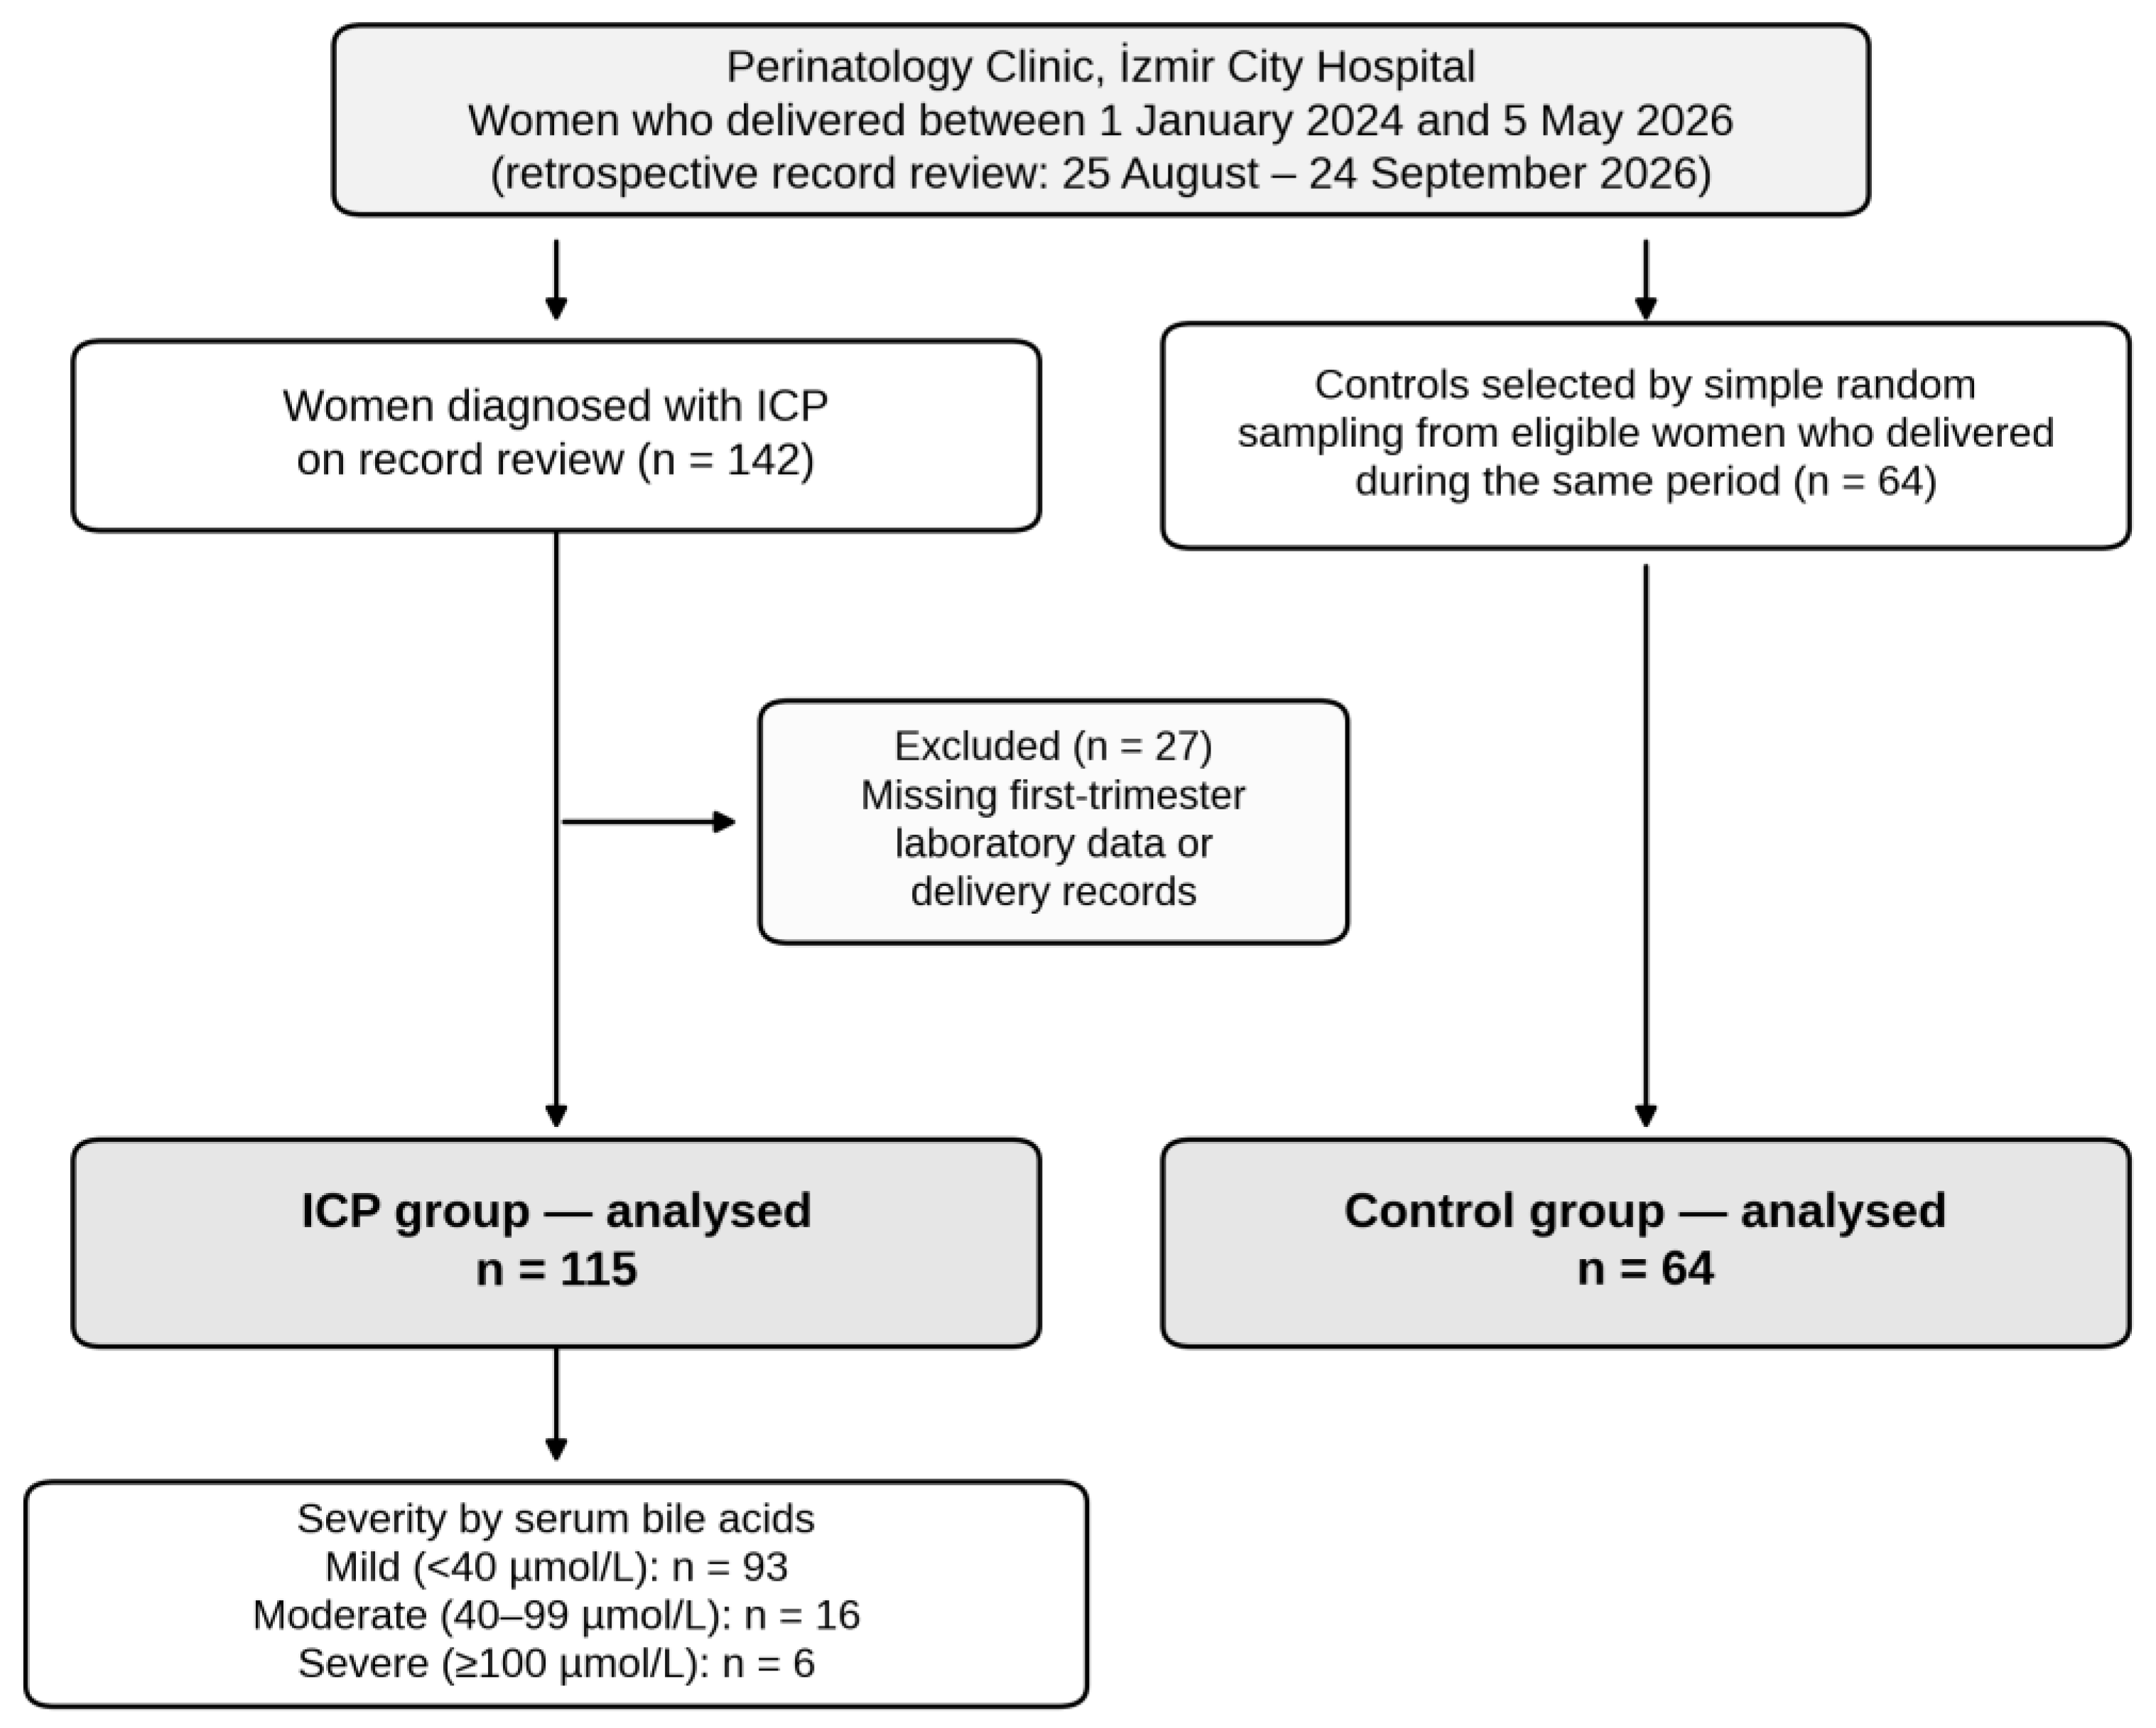
Figure 3.
Distribution of first-trimester systemic immune-inflammation index (SII, A), neutrophil-to-lymphocyte ratio (NLR, B), APRI (C) and FIB-4 (D) in the ICP and control groups. Boxes indicate the interquartile range (Q1–Q3), the thick central line the median and the diamond the mean; whiskers extend to the most extreme observations within 1.5 × IQR, and observations beyond this limit are shown as separate points. p values are from the Mann–Whitney U test. APRI: AST-to-platelet ratio index; FIB-4: fibrosis-4 index.
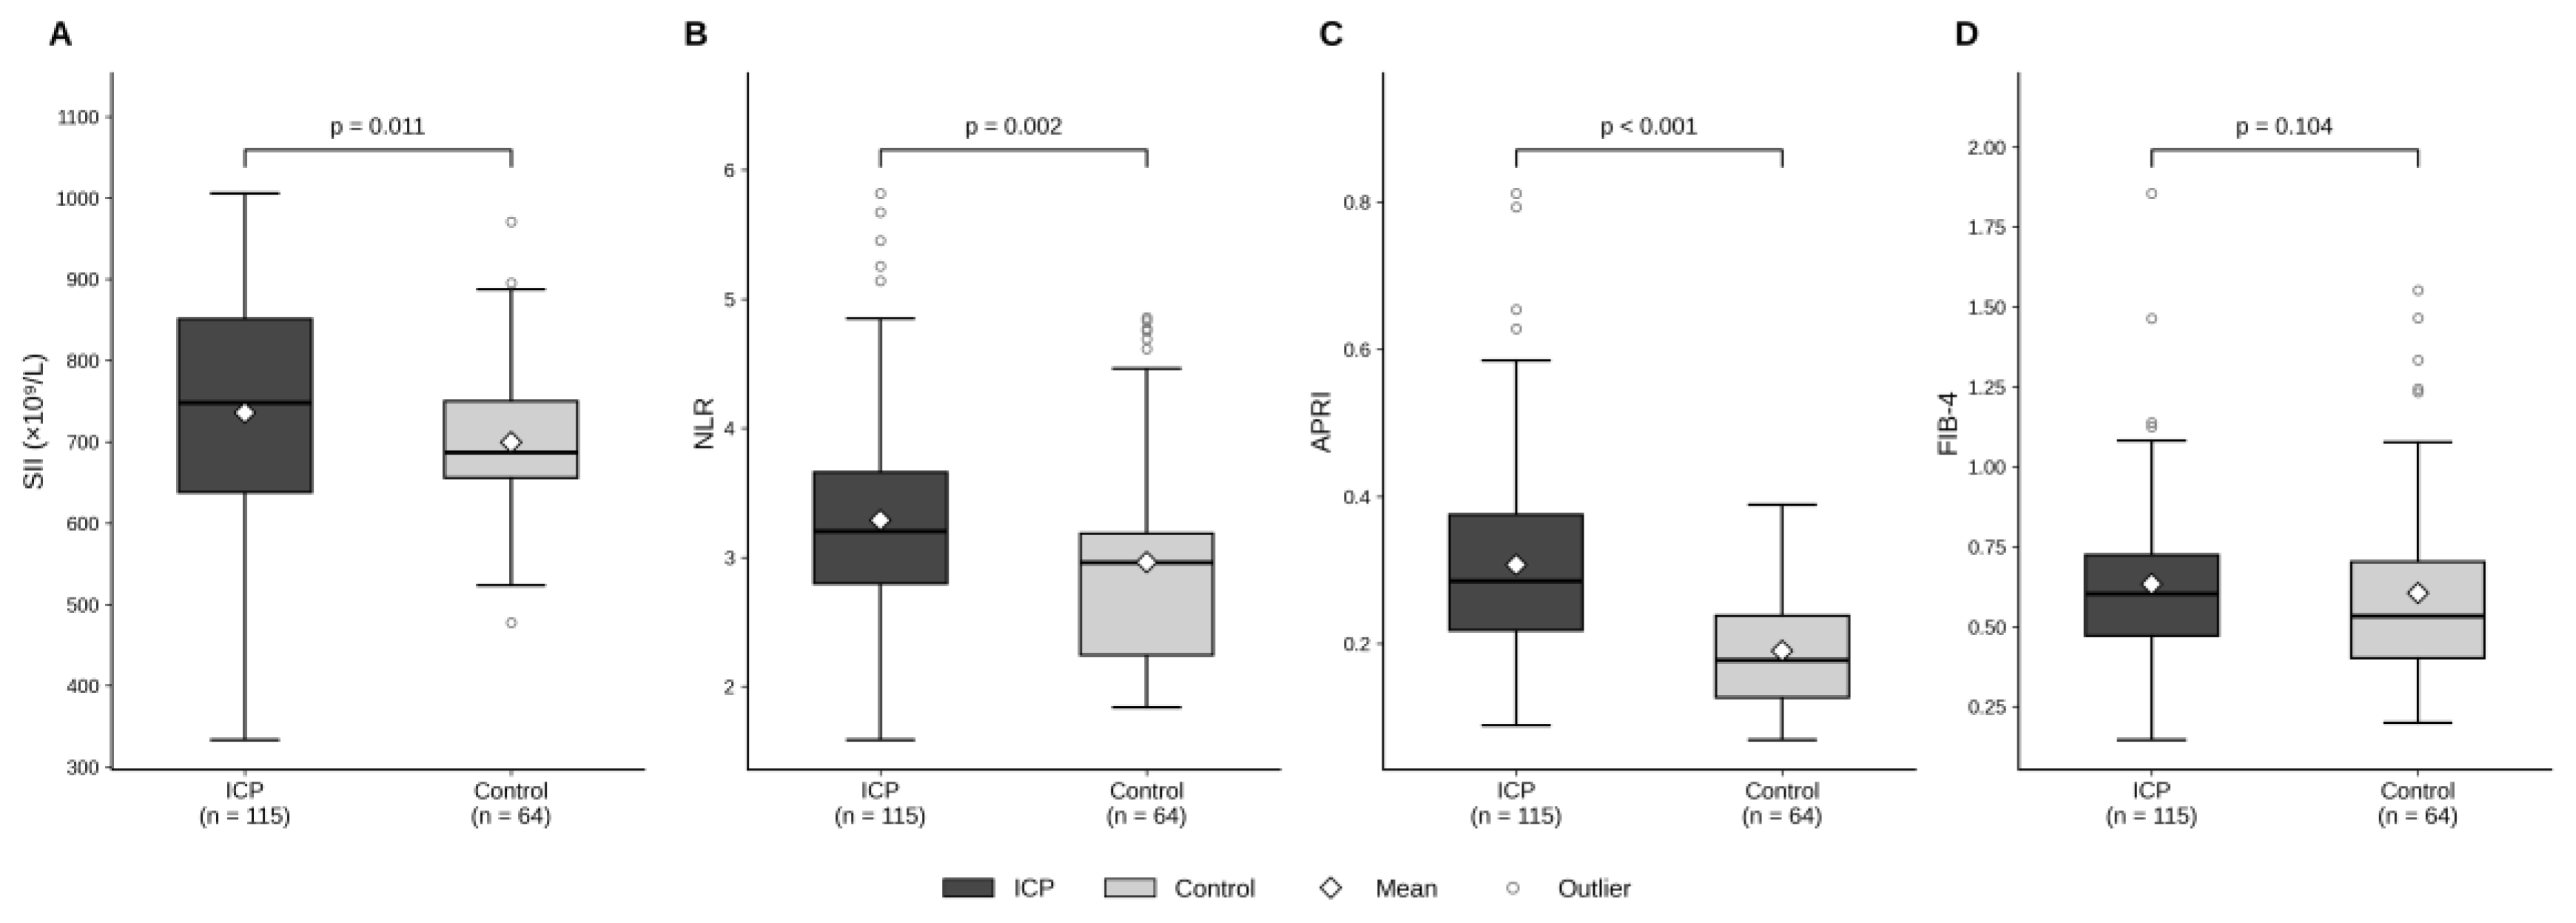
Figure 2.
Receiver operating characteristic (ROC) curves. (A) Discrimination of ICP from healthy pregnancies (n = 179; all markers including PLR); (B) prediction of the composite adverse perinatal outcome in women with ICP (n = 115). The dashed diagonal line indicates the reference line of no discrimination. “Low” indicates that lower values of the marker were associated with the event and that the curve was computed in that direction. AUC: area under the curve.
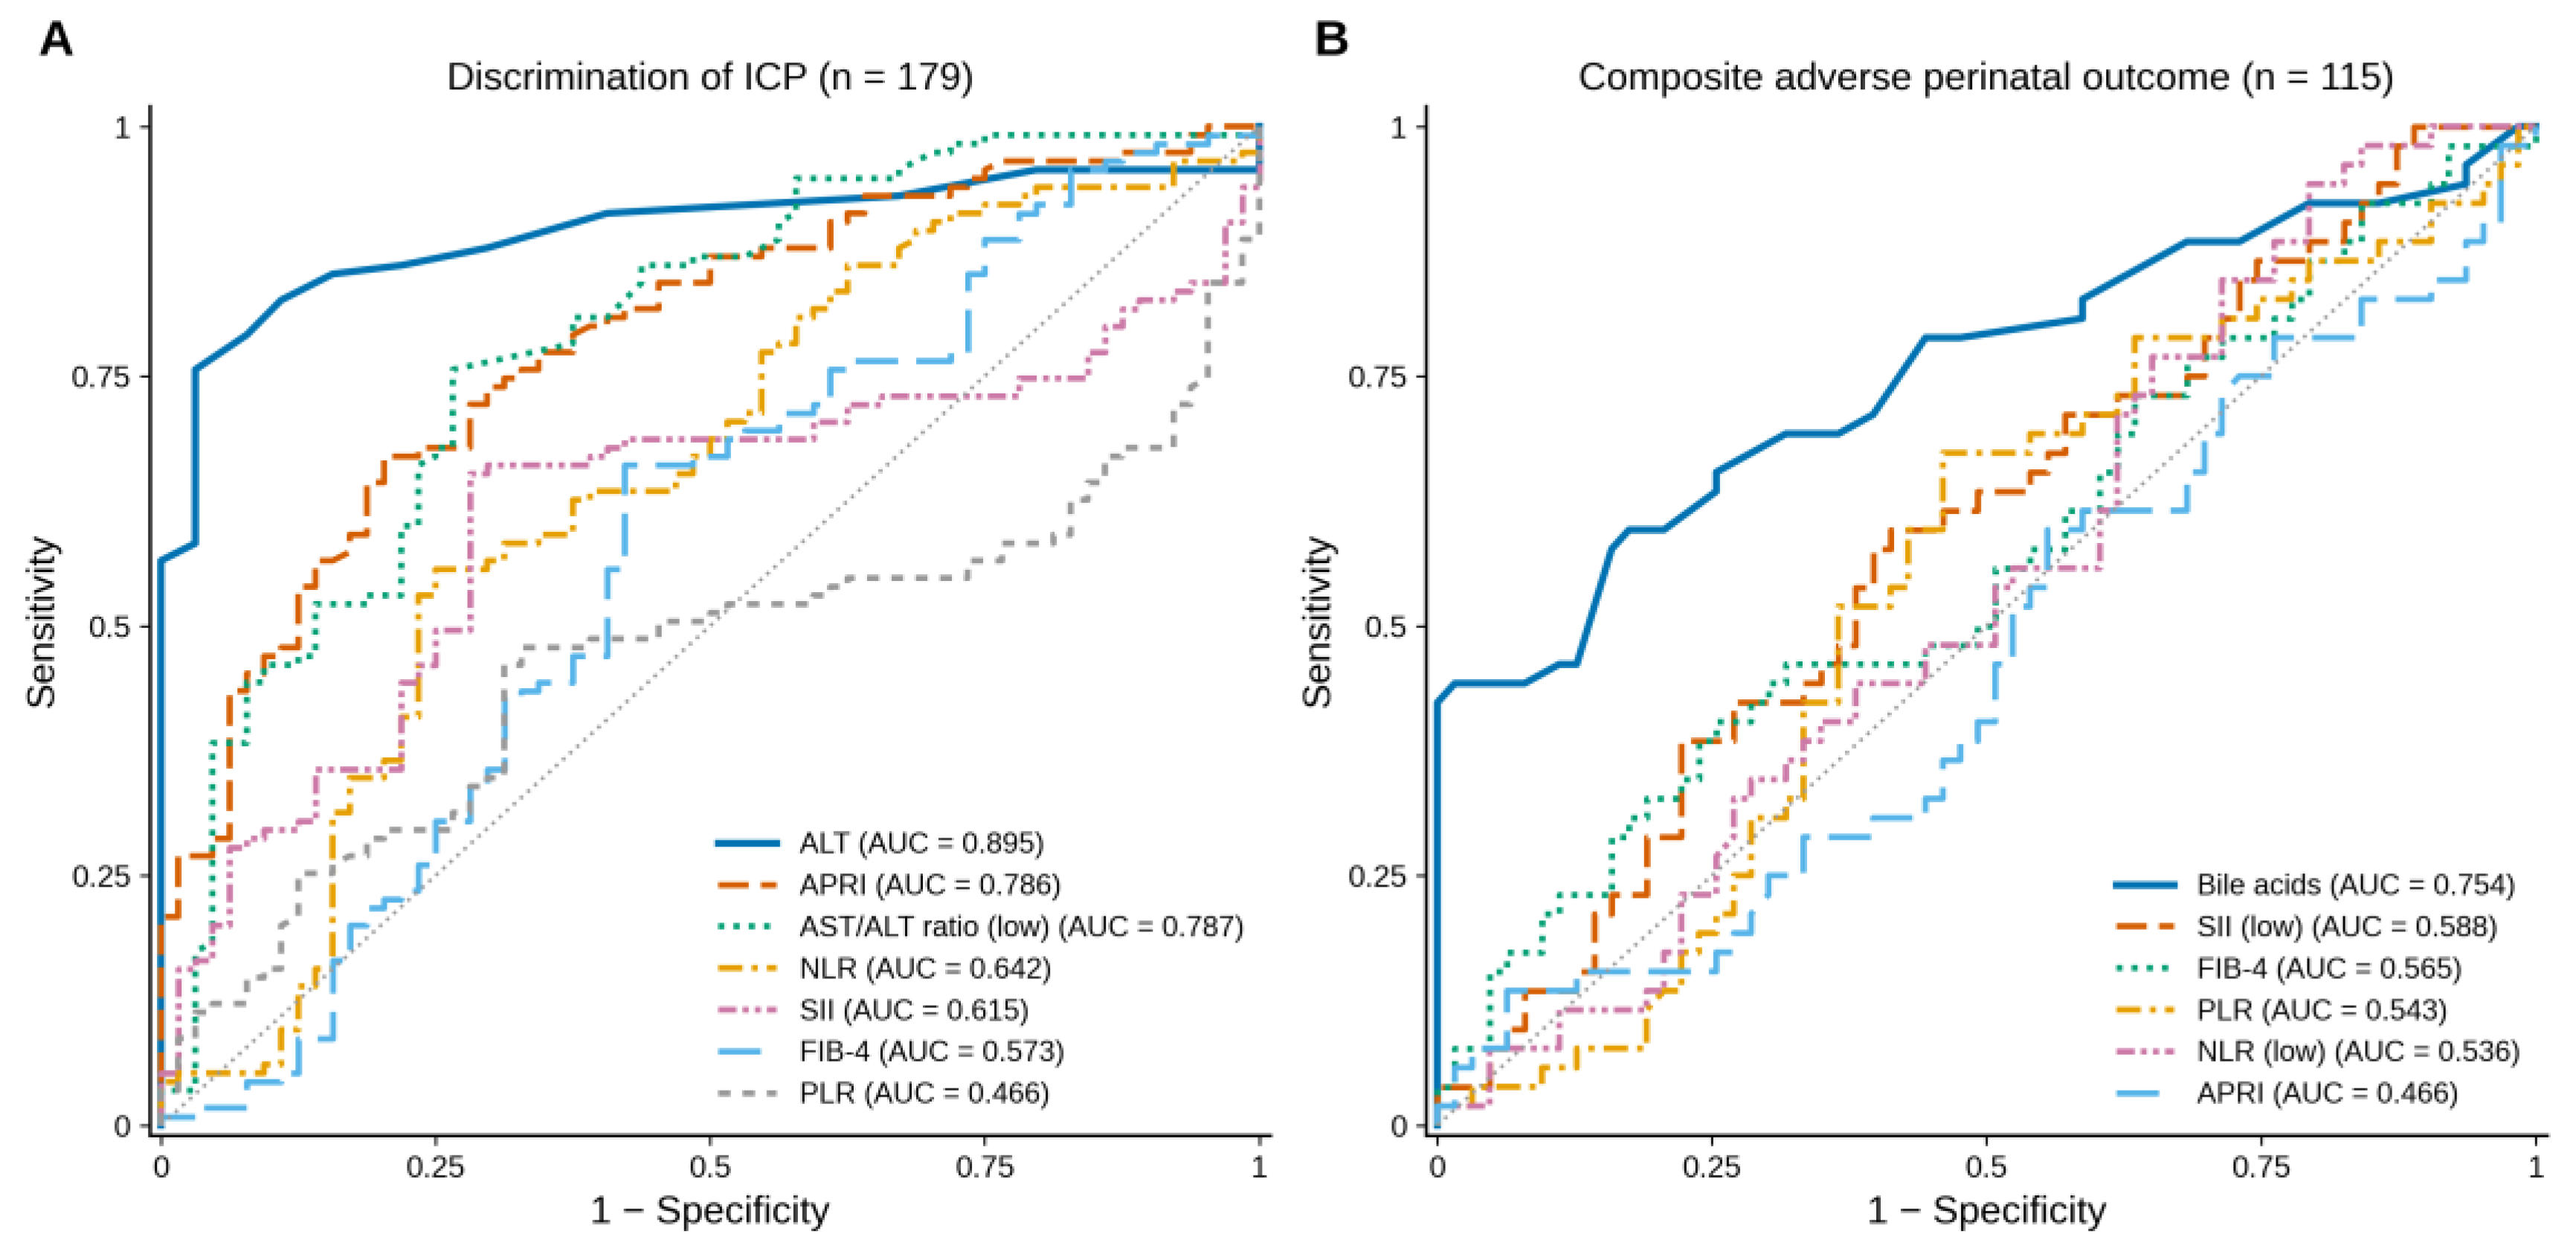
Figure 4.
Gestational age at delivery (A) and birth weight (B) across disease severity groups defined by serum bile acids. Boxes indicate the interquartile range, the thick line the median, the diamond the mean and dots individual women; whiskers extend to the most extreme observations within 1.5 × IQR. p values are from the Kruskal–Wallis test; the dashed horizontal line in (A) marks 37 weeks of gestation. (C) Relationship between serum bile acids and gestational age at delivery; the x-axis is logarithmic, the orange line shows the log-linear fit, and the dashed vertical lines mark the severity thresholds of 40 and 100 µmol/L. The clustering of deliveries at 37 and 36 weeks reflects the institutional delivery-timing protocol. ρ: Spearman correlation coefficient.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.