
Submitted:
09 September 2026
Posted:
18 September 2026
You are already at the latest version
Abstract
Background: Anorexia nervosa (AN) is a severe psycho-metabolic disorder characterized by persistent energy restriction and substantial loss of adipose tissue. Despite profound undernutrition and measurable immune alterations, individuals with acute AN (AN-acute) have been reported to experience fewer clinically evident infections than expected from conventional models of malnutrition. This creates an apparent immune paradox. Scope of Review: Immune findings in AN are heterogeneous, reflecting differences in illness duration, eating-disorder subtype, nutritional severity, and methodology. Furthermore, persistent physical activity, a prominent feature of AN-acute, has received relatively little attention despite its important immunomodulatory effects in healthy individuals. This review presents a hypothesis integrating concepts from exercise physiology and immunometabolism with findings on immune function in AN-acute. Hypothesis: The immune phenotype of AN-acute may reflect selective allocation of limited energy, consistent with immunometabolic principles. It is proposed that severe energy restriction may permit sufficient neutrophil- and macrophage-mediated innate defense to contain pathogens early while constraining the more metabolically demanding activation and expansion of adaptive immunity. Simultaneously, systemic inflammation may remain restrained through multiple metabolic and endocrine mechanisms, potentially reinforced by repeated contraction-derived myokine IL-6 signaling associated with persistent hyperactivity. Conclusion: This model proposes that preserved innate containment, constrained adaptive escalation, and restrained systemic inflammation interact in AN-acute to reduce the clinical expression of infection. It offers a testable framework linking starvation, hyperactivity, immunometabolism, and immune function.
Keywords:
acute anorexia nervosa (AN-acute)
; hyperactivity (HyAc)
; non-exercise activity thermogenesis (NEAT)
; immunometabolism
; leptin
; innate immunity
; adaptive immunity
; inflammation
; myokine interleukin-6
1. Introduction
Anorexia nervosa (AN) is a psychiatric disorder that disproportionately affects females [1,2]. It is characterized by persistent restriction of energy intake despite food availability, resulting in substantial weight loss, approximately 25%, driven primarily by depletion of adipose tissue and reductions in lean mass [3,4]. Semi-starved (SS) famine victims show a comparable degree of weight loss [5].
A striking clinical observation distinguishes AN-acute from starvation syndrome (SS): despite similar degrees of emaciation, individuals with AN-acute remain largely free from clinically apparent viral infections [6,7,8], whereas SS patients experience numerous infections that significantly increase morbidity and mortality [9]. This is unexpected because malnutrition in most contexts reliably increases susceptibility to infectious disease [10].
Reports spanning several decades describe fewer infections than anticipated in AN-acute [11,12] even though immune abnormalities or “dysregulation” are frequently documented [8]. This discrepancy, immune alterations coexisting with a low burden of overt infection, constitutes the AN-acute infection paradox.
Research on immune function in AN has produced heterogeneous and often inconclusive findings [8,13], reflecting variability in illness duration, nutritional severity, metabolic status, and methodological approaches [13]. A largely overlooked factor is persistent physical activity in AN, which may influence immune function through well-established immunomodulatory effects of exercise [14].
This review proposes that immune alterations in AN-acute may represent a functional adaptation rather than simple dysregulation. The underlying assumption is that survival in emaciated AN depends on activating the least energy-consuming physiological processes while still attempting to protect against pathogen invasion.
For this review, AN-acute refers to individuals who are substantially underweight and [15]within the first three years of illness, consistent with the early-stage window identified by Treasure and Russell [15]. It is unclear what changes may occur in AN during a prolonged condition.
The following signals are suggested to be the basis for changes in immune function.
- Low BMI: typically, below 15 kg/m2 in extreme cases and approximately 17 kg/m2 in milder cases [16].
- Reduced daily energy intake: individuals with AN-acute consume approximately 828 kcal/day compared with 2,274 kcal/day in controls, with marked reductions in carbohydrate (151 vs. 324 g/day), fat (12 vs. 78 g/day), and protein (29 vs. 68 g/day) [17]. Despite this profound restriction on caloric intake, it is essential to maintain a certain level of blood glucose to support vital functions, such as brain function. Notably, blood glucose levels generally remain within the low end of the normal range [18]. It should also be noted that to maintain blood glucose levels, the body can break down certain tissue, such as muscle, and convert certain amino acids into glucose.
- Hyperactivity/compulsive movement: Casper et al. [19] found that 95.1% of adolescent females with restricting-type AN reported increased movement drive or restlessness. This is consistent with historical and contemporary observations [20,21,22,23,24]. In this hypothesis, HyAc is regarded as a fundamental aspect of AN-acute, an evolutionarily conserved motor activation pattern linked to starvation and unique to AN-acute [25,26,27,28], with potential effects on multiple physiological systems, including immunity.
The purpose of this review is to integrate evidence from immunology, immunometabolism, starvation physiology, and exercise physiology to examine how the differing energy demands of immune processes may shape immune function in AN-acute. It proposes that adaptations to severe caloric restriction, together with persistent hyperactivity, may selectively preserve some immune functions, constrain others, and restrain systemic inflammation, thereby contributing to the limited clinical expression of infection.
2. Proposed Hypothesis
The central premise is that the infection paradox in AN-acute may be better understood through the principles of energy allocation. Immune responses are metabolically demanding, requiring activation of immune cells, cytokine production, lymphocyte proliferation, antibody synthesis, and tissue repair [29,30]. During prolonged starvation, compounded by elevated movement, these demands must compete for the energy needed to maintain vital physiological functions.
Life History Theory posits that when energy is limited, resources are selectively allocated among competing biological functions to favor immediate survival [31,32]. In this context, energy-efficient immunity refers to preferential use of immune mechanisms that provide meaningful host protection while minimizing metabolic expenditure.
The hypothesis has three components:
1. Innate immune functions may remain relatively preserved under severe energy restriction and may be further influenced by persistent HyAc, allowing early pathogen recognition and containment despite reductions in cell number or selected functions.
2. Adaptive immune activation and clonal expansion may be more strongly constrained because T- and B-cell activation, differentiation, and proliferation require substantial nutrient and biosynthetic investment.
3. An inflammation-restrained systemic environment may emerge from starvation physiology. Persistent HyAc may be an important modifier because repeated physical activity generates autonomic, endocrine, metabolic, thermal, and myokine signals that influence immune function.
Taken together, the model proposes a selective reorganization of host defense under severe energy restriction and persistent HyAc rather than generalized immune failure. This framework is broadly consistent with immune findings reported in AN-acute [6,8] but remains hypothetical and requires direct experimental testing.
The review develops this model by outlining immune organization and immunometabolism, then examining key metabolic regulators, systemic inflammatory signals, innate and adaptive immune function, and the potential modifying role of HyAc in AN-acute.
3. Hyperactivity in Acute Anorexia Nervosa
Persistent HyAc is one of the most characteristic and enduring clinical features of AN-acute. Since Gull’s original description in 1874 [20], excessive physical activity has been consistently documented across patient populations and treatment settings [33,34]. Although often viewed as a secondary behavioral symptom, the present review proposes that HyAc may be central to AN-acute physiology and may exert meaningful immunological effects.
This perspective is important because regular moderate exercise is a potent modulator of immune and inflammatory function in healthy individuals [35]. Understanding the amount, type, and physiological impact of physical activity in AN-acute is therefore essential for evaluating its proposed contribution to the immune phenotype.
3.1. Components of Hyperactivity
In this review, HyAc refers to three related forms of movement that together contribute to total daily activity and energy expenditure [36] and potentially immune function:
- Excessive Exercise (ExEx). Structured, intentional physical activity such as running, cycling, swimming, resistance training, yoga, or organized sports. Intensity and duration vary widely.
- Non-Exercise Activity Thermogenesis (NEAT). Energy expended during routine daily activities outside formal exercise, including walking, shopping, household chores, occupational tasks, standing, and pacing [37]. Because these activities occur repeatedly throughout the day, NEAT can substantially increase total daily activity.
- Spontaneous Physical Activity (SPA). Low-intensity, non-goal-directed movements such as fidgeting, postural adjustments, pacing, and frequent sit-to-stand transitions. SPA is often grouped within NEAT but is distinguished here because these movements may arise spontaneously and reflect an illness-related motor drive rather than deliberate activity [38].
3.2. Physiological Significance of NEAT in AN-Acute
Although NEAT is conventionally distinguished from structured exercise, some forms may impose a meaningful physiological workload in AN-acute. In HCs, increasing workload produces sympathetic activation, raising heart rate (HR) and reducing vagally mediated HRV. Individuals with AN-acute typically show low resting HR and higher parasympathetically mediated HRV [39,40]; yet even mild activity can rapidly alter this pattern. Billeci et al. [41] found that light physical activity elicited marked changes in HR and HRV in adolescents with AN-acute, whereas controls showed minimal autonomic responses. Thus, activities that are physiologically trivial in HCs may represent a greater relative workload in AN-acute.
This is particularly relevant to prolonged walking, which many patients do not recognize as exercise. Kolnes [42] described individuals who walked several hours per day yet denied engaging in exercise. Assessments limited to structured ExEx may therefore underestimate the cumulative physiological impact of repeated low-intensity muscle contractions during NEAT.
A likely explanation for this exaggerated response is reduced aerobic capacity in AN-acute [43], making identical absolute workloads more demanding. Sustained walking and other whole-body NEAT may repeatedly activate sympathetic, endocrine, metabolic, and thermal pathways while increasing energy expenditure. The proposal is not that all NEAT is exercise-like, but that repeated or prolonged whole-body activity may become physiologically significant under severe energy restriction.
3.3. Implications of Hyperactivity for the Present Immune Hypothesis
This broader view of HyAc is central to the proposed immune model. In healthy individuals, regular moderate exercise influences immune cell trafficking, innate and adaptive immune function, and inflammatory regulation [44,45]. Persistent HyAc in AN-acute, including physiologically meaningful NEAT, may therefore provide recurring sympathetic, endocrine, metabolic, thermal, and myokine signals that shape immune function.
These effects are particularly relevant to mechanisms discussed later, including muscle-derived IL-6, cortisol, neutrophil mobilization, immunometabolic signaling, and activity-induced warming. If confirmed, assessments limited to structured exercise may underestimate both the physiological burden of HyAc and its contribution to the immune phenotype of AN-acute.
4. The Immune System
4.1. Evolutionary Organization of the Immune System
The immune system comprises two highly integrated branches: innate and adaptive immunity. Innate immunity is evolutionarily ancient and provides the immediate foundation of host defense, whereas vertebrate adaptive immunity emerged approximately 500 million years ago, adding highly specific antigen recognition and immunological memory. Although the two systems differ in evolutionary origin, speed, specificity, and mechanisms of activation, they function cooperatively, with innate immune signals helping to initiate and shape adaptive responses [46,47]. These evolutionary and metabolic differences provide important background for the hypothesis proposed in this review.
4.2. Functional Organization of the Immune System
Innate immunity provides the body’s immediate defense against invading pathogens by recognizing conserved microbial or damage signals and rapidly initiating antimicrobial activity, inflammation, clearance, and repair [48]. Innate responses are not inherently pro-inflammatory; depending on the physiological context, they may promote inflammatory defense, metabolic regulation, resolution, or tissue repair.
Adaptive immunity provides highly specific protection through antigen-specific T and B lymphocytes and generates long-lasting immunological memory [49]. During a novel infection, rare antigen-specific lymphocytes must first be activated and then undergo extensive clonal expansion and differentiation before a substantial adaptive response develops [50].
The two systems are closely linked by dendritic cells (DCs), which capture microbial antigens during innate surveillance and, following appropriate activation, initiate adaptive immunity by activating naïve T cells [51]. This DC–T-cell transition is central to the present hypothesis, because metabolic constraint at this point could limit adaptive upregulation while leaving substantial innate function available.
4.3. Energetics of Innate and Adaptive Immunity
Both innate and adaptive immune cells increase their metabolic activity during activation, making immune function sensitive to nutrient and energy availability [29,30]. The important distinction is not that innate immunity is metabolically inexpensive, but that many innate effector cells are already present and can respond rapidly, whereas a primary adaptive response requires activation and extensive clonal expansion of antigen-specific lymphocytes.
Full adaptive upregulation therefore requires sustained nutrient uptake, biosynthesis, cellular growth, and repeated cell division. Under severe and prolonged energy restriction, this additional metabolic investment may make adaptive expansion particularly vulnerable to constraint.
This leads to a central proposal of the present model: in AN-acute, limited resources may permit sufficient rapid innate defense while restricting progression to the greater metabolic investment required for adaptive expansion. The specific roles of neutrophils, macrophages, and dendritic cells in maintaining early innate defense, as well as the potential metabolic constraint at the DC–T-cell transition, are considered in later sections.
5. Immunometabolism during Energy Restriction
Metabolism refers to the biochemical processes that convert nutrients into energy, such as ATP, and into molecules required for cellular function. Immune cells use several metabolic pathways and adjust their fuel use according to nutrient availability and functional demands. Their ability to activate, proliferate, differentiate, produce cytokines, and perform effector functions is therefore shaped by both the availability of metabolic fuels and the capacity to activate the metabolic pathways required for each response. (Figure 1).
5.1. Immunometabolism: Metabolism as a Regulator of Immune Function
Immunometabolism examines how metabolism and energy availability regulate immune-cell function. Metabolic conditions influence whether immune cells remain quiescent, activate, proliferate, migrate, produce inflammatory mediators, repair tissue, or form long-term memory. Thus, metabolism provides not only fuel but also signals that govern immune-cell behavior [29,30].
This concept is particularly relevant to AN-acute, where prolonged energy restriction combined with persistent HyAc creates sustained metabolic stress and may strongly influence how immune cells allocate and use limited resources.
5.2. Energy Availability and Metabolic Fuels
Immune cells use substrates such as glucose, fatty acids, and amino acids to generate ATP and provide the cellular building blocks required for immune function. The availability of these fuels can therefore influence both the magnitude and character of an immune response [29,30].
During prolonged energy restriction, immune cells must adjust their metabolism to balance immediate functional demands with cellular maintenance and survival. This metabolic flexibility may allow some functions to continue even when the resources required for more extensive activation or proliferation are limited.
5.3. Major Metabolic Pathways
Immune cells use several metabolic pathways, of which glycolysis and oxidative phosphorylation are particularly important [29,30].
Glycolysis rapidly converts glucose into ATP and metabolic intermediates that support rapid immune activation and biosynthesis. Many immune cells increase glycolysis when rapid functional responses, growth, or proliferation are required.
Oxidative phosphorylation (OXPHOS) occurs within mitochondria, uses predominantly fats (free fatty acids) as fuel, and produces substantially more ATP per unit of fuel. It commonly supports cellular maintenance, sustained function, and many regulatory or memory states.
The relative importance of these pathways varies among immune-cell types and functional states. Neutrophils, for example, rely heavily on glycolysis even at baseline, whereas lymphocytes and macrophages can reprogram their metabolism following activation.
5.4. Metabolic Reprogramming during Immune Activation
A major advance in immunology has been the recognition that immune cells reprogram their metabolism according to functional demands. Activation often increases nutrient uptake and glycolysis, whereas other functions may depend more strongly on mitochondrial metabolism, fatty-acid oxidation, or combinations of pathways [29,30]. These metabolic programs help shape inflammatory, regulatory, antimicrobial, and tissue-repair functions.
This principle is especially relevant to adaptive immune upregulation. A primary T- or B-cell response requires antigen-specific lymphocytes to activate, proliferate, differentiate, and undergo extensive clonal expansion. These processes require substantial increases in nutrient uptake, protein synthesis, lipid and nucleotide biosynthesis, and overall metabolic activity [30,52]. Prolonged energy deficiency may therefore be particularly important for adaptive expansion, not because innate immunity is metabolically inexpensive, but because a substantial primary adaptive response requires generating large numbers of new antigen-specific cells.
5.5. Implications for AN-Acute
This framework underlies a central hypothesis of the present review. How immune cells recognize and respond to this limited energy availability depends on several interacting metabolic signals. Three particularly relevant regulators are leptin, AMP-activated protein kinase (AMPK), and mechanistic target of rapamycin complex 1 (mTORC1).
6. Key Metabolic Regulators of Immune Function
6.1. Leptin: A Systemic Signal of Energy Availability
Leptin is an adipocyte-derived hormone with cytokine-like properties whose circulating concentration broadly reflects body-fat stores. Individuals with AN-acute therefore develop profound hypoleptinemia as adipose tissue is depleted [53,54].
Low leptin is an important systemic signal of energy deprivation. In the hypothalamus, falling leptin concentrations contribute to suppression of energetically costly reproductive and thyroid functions and to other neuroendocrine adaptations that help conserve energy during prolonged starvation [55] .
Leptin also links nutritional status to immune function. Adequate leptin signaling supports T-cell activation, proliferation, cytokine production, effector differentiation, and the metabolic reprogramming required to sustain these processes [56,57]. Experimental starvation is associated with reduced leptin and impaired T-cell responses, whereas leptin replacement can restore aspects of T-cell function [56]. Particularly relevant to the present hypothesis, leptin has been described as metabolically “licensing” activated T cells by supporting the increased glucose uptake and metabolic activity required for proliferation and effector function [57].
B-cell survival, proliferation, differentiation, and antibody production are also influenced by leptin and by the broader nutritional and metabolic environment [58]. Thus, profound hypoleptinemia could potentially influence both major arms of adaptive immunity rather than T-cell responses alone.
Leptin also influences innate immune cells, including neutrophils, monocytes/macrophages, and dendritic cells; profound hypoleptinemia should therefore not be viewed as selectively affecting adaptive immunity [58] . However, many immediate innate antimicrobial functions can be performed by cells already present and do not require the extensive clonal proliferation characteristic of a primary adaptive response. Substantial adaptive upregulation, by contrast, requires antigen-specific lymphocytes to activate, proliferate, differentiate, and undergo extensive clonal expansion.
In AN-acute, very low leptin may therefore contribute to a metabolic environment in which selected innate functions remain available while full adaptive expansion becomes more difficult to initiate and sustain. This interpretation remains hypothetical because leptin-dependent metabolic signaling in immune cells has not been directly characterized in AN-acute.
6.2. AMPK: The Intracellular Energy-Stress Sensor
AMP-activated protein kinase (AMPK) is a central intracellular energy sensor that is activated/increased when cellular energy availability declines, as reflected by changes in the ATP/AMP/ADP balance. Once activated, AMPK acts as a metabolic brake on energy-intensive processes: it suppresses anabolic activities such as cell growth and protein synthesis while promoting ATP-generating pathways and cellular maintenance and survival [59,60].
Under conditions of adequate energy availability, AMPK activity need not constrain the metabolic reprogramming required for immune activation. When cellular energy becomes limited, however, increased AMPK signaling shifts resources away from growth and biosynthesis toward energy conservation. One important mechanism of AMPK is the inhibition of mTORC1, a nutrient-sensitive pathway that promotes cell growth and biosynthesis [60,61]
This is particularly relevant to lymphocyte activation. When T cells are activated, they require much more energy and nutrients to grow and multiply. During nutrient limitation, elevated AMPK helps them conserve energy and adapt to reduced fuel availability [62]. However, it can also restrict the energy-consuming processes required for extensive T-cell proliferation [62]. Thus, elevated AMPK is better understood not simply as an inhibitor of immune activation, but as a metabolic checkpoint that helps match the scale of the immune response to available cellular energy.
A similar pattern may occur in AN-acute. Severe caloric restriction produces sustained systemic energy scarcity, while persistent HyAc places additional demands on already limited fuel supplies. Together, starvation and continued activity could favor energy-stress signaling in immune cells, potentially increasing reliance on AMPK-dependent pathways that support cellular maintenance and metabolic adaptation while constraining metabolically costly processes such as sustained lymphocyte growth and clonal expansion.
Importantly, increased AMPK activity in immune cells has not been directly demonstrated in AN-acute. Its proposed role in this model therefore remains hypothetical. Nevertheless, AMPK interacts closely with the nutrient-sensitive mTORC1 pathway and provides an important mechanistic link between cellular energy status and the metabolic requirements of immune activation [60,61,63].
6.3. Mechanistic Target of Rapamycin Complex 1 (mTORC1)
mTORC1 is a central nutrient- and growth-sensing pathway that integrates signals from amino acids, growth factors, hormones, and cellular energy availability. Functionally, it can be considered a “growth permission” signal: when nutrients and energy are sufficient and permissive hormonal signals are present, mTORC1 supports protein synthesis, cellular growth, activation, and proliferation; when resources are scarce, its activity declines [64].
This pathway is particularly important during T-cell activation, which requires a major increase in nutrient uptake and biosynthetic capacity [30]. Reduced mTORC1 signaling during nutrient deprivation can therefore constrain T-cell differentiation and proliferation. Importantly, experimental starvation and reduced leptin signaling have been shown to decrease mTOR activity and impair CD4+ effector T-cell proliferation [65].
AMPK and mTORC1 function as opposing but coordinated regulators of cellular resource use. When energy and nutrient availability are sufficient, mTORC1 supports anabolic growth and immune cell activation. During cellular energy stress, increased AMPK signaling can restrain mTORC1 and reduce energy-consuming biosynthesis [59,61].
In AN-acute, severe caloric restriction, reduced nutrient availability, profound hypoleptinemia, and persistent HyAc could collectively favor increased AMPK and reduced mTORC1 signaling. Such an environment may be particularly consequential for adaptive immunity because activation and clonal expansion require sustained nutrient uptake, biosynthesis, and cell growth [30,66].
Despite these constraints, during low energy availability, relatively quiescent naïve and memory T and B cells may be maintained because their basic survival requires substantially less energy than their activation, differentiation, and extensive clonal expansion. Thus, the adaptive immune system may remain present but have a reduced capacity to mount a large new response. This interpretation is consistent with the continued presence of lymphocytes in AN-acute despite reported alterations in lymphocyte populations and activation characteristics [8,67].
Studies of immune-cell numbers and functional responses in AN-acute have, however, yielded heterogeneous findings, with some cells and functions remaining relatively preserved [8,67,68]
Moreover, altered AMPK–mTORC1 signaling has not been directly demonstrated in immune cells from individuals with AN-acute. The proposed AMPK↑–mTORC1↓ metabolic constraint should therefore be regarded as a biologically plausible and testable component of the present hypothesis rather than an established feature of AN.
7. Systemic Signals Shaping Inflammation and Fuel Allocation in AN-Acute
7.1. Cytokine Patterns and the Limits of Interpreting Inflammation in AN-Acute
Circulating cytokines provide valuable information about immune activity, but cytokine concentrations alone do not define the overall inflammatory state. Cytokine findings in AN-acute are heterogeneous. Meta-analytic evidence indicates that IL-6 is elevated in AN, while findings for other inflammatory cytokines are less consistent [69]. Thus, the available evidence does not support a uniformly pro-inflammatory state.
An important limitation is that cytokines are commonly measured from single resting or fasting blood samples without adequately accounting for recent physical activity. This is particularly relevant to IL-6 because skeletal muscle can release substantial amounts of myokine IL-6 during contraction [70].
7.2. IL-6 Source Matters: Immune-Derived Versus Muscle-Derived Signaling
Elevated circulating IL-6 is frequently reported in AN-acute and is often interpreted as evidence of inflammation. However, circulating IL-6 concentration alone cannot determine its biological function, as IL-6 has various sources. During infection or tissue injury, IL-6 is produced by immune cells as part of a broader inflammatory response, typically accompanied by cytokines such as IL-1β and TNF-α. In contrast, contracting skeletal muscle releases the same IL-6 molecule into the circulation, where it functions as a myokine with important metabolic and inflammation-limiting actions [70].
Furthermore, different signaling pathways shape the functional profile of IL-6. In classical signaling, IL-6 binds to membrane-bound IL-6 receptors on a restricted set of cells, including hepatocytes and select leukocyte subsets. This pathway is generally associated with metabolic regulation, regenerative responses, and short-lived anti-inflammatory effects. In pro-inflammatory trans-signaling, IL-6 binds to soluble IL-6 receptors in the circulation, enabling IL-6 to act on a much broader range of cells. This pathway promotes leukocyte recruitment and sustained inflammatory activity and is considered the pro-inflammatory arm of IL-6 biology [71].
Exercise-induced IL-6 can increase markedly, particularly during prolonged activity; increases approaching 100-fold have been reported after strenuous endurance exercise, although smaller increases are more common [70]. Persistent HyAc in AN-acute, including prolonged walking and repeated bouts of activity, therefore provides a plausible recurring stimulus for skeletal-muscle IL-6 release.
The present hypothesis proposes that a substantial, and potentially predominant, component of the elevated circulating IL-6 in AN-acute may be muscle-derived rather than a marker of conventional systemic inflammation. Persistent HyAc could repeatedly generate the myokine IL-6, whose physiological effects favor metabolic regulation and limit inflammatory amplification. A relative predominance of classical over pro-inflammatory trans-signaling is also plausible within this model, but neither the tissue source of circulating IL-6 nor the balance between these signaling pathways has been directly established in AN-acute.

Table 1.
Comparison of inflammation-associated IL-6 and contraction-induced muscle IL-6 myokine. Inflammation-associated IL-6 and muscle-derived IL-6 are the same protein. Their differing effects reflect their sources, stimuli, concentrations, durations, receptor pathways, and surrounding cytokine environments.
| Feature | Inflammation-associated IL-6 | Contraction-induced muscle IL-6 myokine | Selected references |
| Meaning of the term | IL-6 acts as an immune-signaling cytokine during infection, injury, or inflammation. | The same IL-6 molecule is released by contracting skeletal muscle; the term “myokine” denotes its muscular source. | [70] |
| Principal source | Mainly immune cells, including macrophages, monocytes, and fibroblasts. | Primarily contracting skeletal muscle fibers. | [70] |
| Principal stimulus | Pathogens, tissue damage, TNF-α, and IL-1β. | Muscle contraction, low muscle glycogen, increased energy demand, adrenergic stimulation. | [70] |
| Predominant signaling pattern | Persistent trans-signaling strongly associated with leukocyte recruitment and chronic inflammation. | More often associated with short-lived local and classic signaling. | [71] |
| Typical temporal pattern | Rises during infection or injury and may remain elevated as long as the inflammatory stimulus persists. | Rises during exercise, peaks near the end or shortly after activity, then declines. | [70] |
| Duration of exposure | May be prolonged or chronic. | Usually brief, pulsatile, and transient. | [70] |
| Magnitude | Ranges from modest, persistent elevation to marked increases during severe infection or trauma. | May increase dramatically, sometimes approaching 100-fold during prolonged strenuous exercise. | [70] |
| Impact on metabolism | Persistent elevation may accompany insulin resistance and metabolic dysfunction. | Mobilizes fuel by increasing glucose availability, lipolysis, and fatty-acid oxidation. | [70] |
| Impact on inflammation | Can promote or maintain inflammation when persistent and combined with TNF-α, IL-1β, and chemokines. | Often has indirect anti-inflammatory effects by increasing IL-1ra, IL-10, and cortisol and reducing TNF-α. | [70] |
| Impact on innate and adaptive immunity | Supports innate defense and shapes adaptive responses; persistent signaling may contribute to autoimmune inflammation. | May help regulate innate inflammation and indirectly restrain excessive adaptive immune activation; direct effects remain context-dependent. | [71] |
| Impact on acute-phase proteins | Sustained IL-6 strongly stimulates hepatic acute-phase protein production, including CRP. | Brief exercise-induced IL-6 may produce only limited or transient acute-phase responses. | [90] |
| Impact on fever | Contributes to fever via hypothalamic prostaglandin E2 signaling during inflammation. | Usually does not produce fever when released transiently during exercise. | [70,90] |
| Impact on sickness behavior | Alongside IL-1β, TNF-α, and prostaglandins, may contribute to fatigue, reduced appetite, lethargy, and social withdrawal. | Does not normally produce the full sickness-behavior response associated with infection. | [70,90] |
Notes: APP = acute-phase proteins; CRP = C-reactive protein; IL-1ra = interleukin-1 receptor antagonist; TNF-α = tumor necrosis factor alpha. Abbreviations: APPs, acute-phase proteins; CRP, C-reactive protein; IL-1β, interleukin-1 beta; IL-1ra, interleukin-1 receptor antagonist; IL-10, interleukin-10; IL-6, interleukin-6; PGE2, prostaglandin E2; TNF-α, tumor necrosis factor alpha.
7.3. Myokine IL-6 as a Link Between Hyperactivity, Fuel Mobilization, and Inflammation Restraint
Muscle-derived IL-6 may perform two particularly relevant functions.
- First, it contributes to the exercise-induced anti-inflammatory response by increasing mediators such as IL-1 receptor antagonist and IL-10, and by limiting TNF-α production [70].
In AN-acute, repeated myokine IL-6 signaling could therefore help mobilize scarce metabolic fuels while simultaneously restraining unnecessary inflammatory amplification. This provides a potential mechanistic link between persistent HyAc, metabolic adaptation, and the inflammation-restrained systemic phenotype proposed in this review.
Future studies should determine the source and signaling characteristics of circulating IL-6 in AN-acute and relate these to recent physical activity, additional inflammatory markers, and metabolic responses. Measurements before and after both structured exercise and prolonged low-intensity activity would be especially informative.
Whereas myokine IL-6 may help coordinate fuel use during continued activity, cortisol may complement these adaptations by mobilizing stored substrates while also restraining inflammatory signaling.
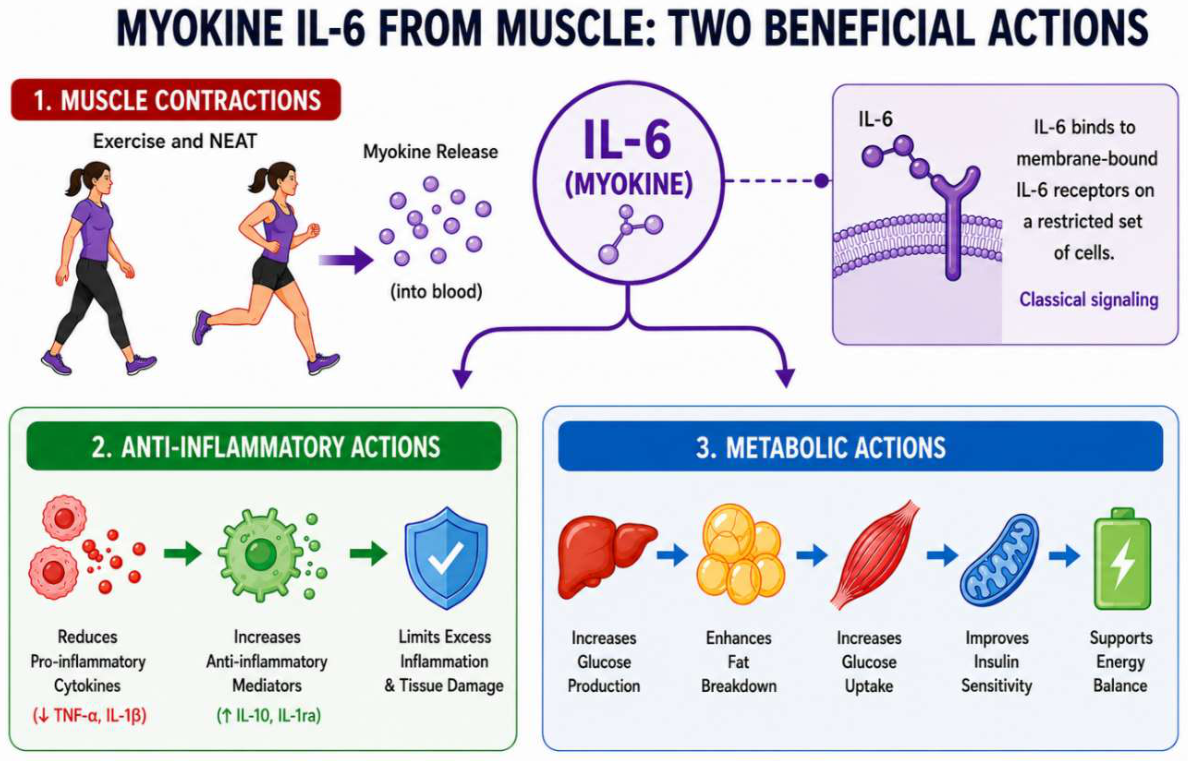
Figure 2.
Muscle-derived IL-6 released during contraction may exert coordinated anti-inflammatory and metabolic effects.
Figure 2.
Muscle-derived IL-6 released during contraction may exert coordinated anti-inflammatory and metabolic effects.
7.4. Hypercortisolemia: Inflammation Restraint and Fuel Mobilization
Hypercortisolemia is one of the most consistent endocrine abnormalities in AN-acute. A systematic review and meta-analysis of 101 studies involving more than 2,500 females found significantly higher cortisol concentrations in women with AN-acute than in normal-weight controls [73]. Severe energy deficiency activates the hypothalamic–pituitary–adrenal axis, and persistent HyAc may serve as an additional physiological stressor [74].
Cortisol has two broad actions that are central to the present hypothesis. First, it acts on the immune system by restraining inflammatory and adaptive immune activation and has multiple effects on innate functions. Cortisol reduces pro-inflammatory cytokine signaling (e.g., IL-1β, TNF-α, IL-6) and limits several adaptive immune processes, including lymphocyte activation, differentiation, and proliferation [75].
Cortisol has selective effects on innate immune cells and reshapes innate immunity in several coordinated ways. It rapidly mobilizes neutrophils from the bone marrow into circulation yet simultaneously reduces their ability to exit the bloodstream and enter tissues. As a result, neutrophils appear elevated in blood tests but are less effective at participating in local inflammation. It also suppresses pro-inflammatory activity in monocytes and macrophages, reducing the production of cytokines such as IL-1β and TNF-α. At the same time, it promotes a shift toward anti-inflammatory, tissue-maintenance macrophage phenotypes (M2-like). Dendritic cell maturation and antigen-presenting capacity are likewise inhibited, further reducing the initiation of adaptive immune responses [75].
In this way, glucocorticoids do not simply “switch off” immunity; they redistribute and restrain innate and adaptive immune activity to prevent excessive or energetically costly inflammatory responses [75].
Second, cortisol plays a central role in metabolism by maintaining the body’s energy supply during starvation and physiological stress. It helps the liver generate new glucose and mobilizes stored fuels by breaking down muscle protein and releasing fatty acids from adipose tissue. These processes increase the availability of amino acids, glycerol, and fatty acids, materials that are converted into energy when food intake is extremely limited. Cortisol also reduces glucose utilization in less critical tissues, thereby preserving circulating glucose for organs with immediate metabolic needs, such as the brain [76,77].
Within the present hypothesis, hypercortisolemia in AN-acute may therefore serve a dual function: restraining energetically costly inflammatory activity while maintaining access to metabolic fuel during severe energy scarcity. By dampening adaptive immune responses, modulating aspects of innate immunity, and mobilizing internal energy stores, cortisol may contribute to both limited immune upregulation and the strategic redistribution of scarce resources toward essential physiological demands.
7.5. Elevated Adiponectin: Fuel Efficiency, Inflammation Restraint, and Macrophage Regulation
Adiponectin is an adipocyte-derived hormone with important metabolic and immune-regulatory functions. Unlike leptin, which declines markedly with adipose tissue loss, circulating adiponectin is paradoxically elevated in AN-acute. Pannacciulli et al. [78] reported significantly higher adiponectin concentrations in women with AN-acute.
Adiponectin may be particularly relevant during prolonged energy restriction because it promotes fatty-acid oxidation, enhances insulin sensitivity, and supports metabolic fuel utilization in active tissues [79,80]. These actions may help optimize the use of limited metabolic substrates.
Adiponectin also has important inflammation-limiting effects. It can reduce macrophage production of pro-inflammatory mediators such as TNF-α and IL-6, increase anti-inflammatory mediators including IL-10, and promote macrophage characteristics associated with tissue repair and resolution of inflammation [81].
Within the present hypothesis, elevated adiponectin in AN-acute may therefore contribute to more efficient fuel utilization and restraint of excessive inflammatory activity, including modulation of macrophage function. Its elevation is therefore consistent with, rather than proof of, the proposed inflammation-limiting immunometabolic state of AN-acute.
7.6. Ketone Bodies: Alternative Fuel and Selective Inflammatory Restraint
Ketone bodies rise during prolonged caloric restriction as the body shifts from greater reliance on glucose toward increased use of stored fat. The principal circulating ketone, β-hydroxybutyrate (BHB), functions both as an alternative fuel during starvation and as a metabolic signaling molecule. Ketone production also increases during fasting and prolonged exercise, particularly when carbohydrate availability is limited [82].
BHB suppresses specific innate inflammatory pathways. Most notably, it inhibits an inflammasome, a danger-sensing complex in macrophages and other innate immune cells that normally promotes production of the pro-inflammatory cytokines IL-1β and IL-18 [83]. BHB may therefore reduce inflammatory amplification.
Ketone bodies can also be elevated in individuals with AN-acute during severe caloric restriction [84]. Persistent HyAc could potentially further increase ketone production and utilization under conditions of limited carbohydrate availability [85].
Within the present hypothesis, increased ketone availability could therefore have two complementary effects: providing an alternative metabolic fuel when glucose is scarce and selectively restraining excessive inflammatory signaling [82,83]. BHB may therefore contribute to the proposed inflammation-limiting immunometabolic state of AN-acute, although its specific role in AN-acute and the extent to which HyAc modifies these effects remain hypothetical.
8. Cellular Maintenance, Damage Control, and Inflammatory Resolution in AN-Acute
8.1. Autophagy: Recycling, Survival, and Immune-Cell Maintenance
Autophagy is an intracellular recycling system that breaks down damaged proteins, mitochondria, and other cellular components so their constituents can be reused. During nutrient deprivation, this can provide metabolic substrates while removing damaged material that might otherwise impair cellular function or promote inflammation [86].
Autophagy is also important for immune-cell survival and homeostasis. In T cells, it helps maintain mitochondrial quality, metabolic stability, and long-term survival and contributes to memory-cell formation. Autophagy similarly supports B-cell development and survival [87]. Thus, during prolonged energy restriction, autophagy could potentially help maintain existing T- and B-cell populations even when the greater metabolic investment required for activation and clonal expansion is constrained.
These functions may be particularly relevant in AN-acute because nutrient deprivation increases reliance on autophagic recycling. Additionally, exercise can stimulate autophagy and mitophagy, particularly in skeletal muscle, helping remove damaged proteins and mitochondria and support adaptation to repeated metabolic stress [88].
Within the present hypothesis, severe caloric restriction and persistent HyAc may therefore increase reliance on autophagy to conserve limited substrates, maintain cellular integrity, and support the survival of existing immune cells.
8.2. Apoptosis: Controlled Removal of Damaged or Infected Cells
Apoptosis is a controlled form of programmed cell death that removes damaged, stressed, infected, or unnecessary cells. Unlike cells undergoing uncontrolled rupture, apoptotic cells remain largely contained and display molecular “eat-me” signals that identify them for removal. This permits the elimination of damaged cells with little inflammatory disruption [89].
In AN-acute, prolonged energy restriction combined with persistent activity may increase cellular and mitochondrial stress. When damage becomes too extensive for repair or autophagic recycling, apoptosis provides a controlled mechanism for removing compromised cells without the inflammatory consequences associated with uncontrolled necrosis.
8.3. Efferocytosis: Clearance of Apoptotic Cells and Inflammatory Resolution
Efferocytosis is the subsequent recognition and clearance of apoptotic cells by macrophages and other phagocytes. This process prevents dying cells from rupturing and releasing inflammatory contents and promotes macrophage responses associated with resolution and tissue repair [89].
Within the present model, efficient efferocytosis could therefore complement apoptosis by rapidly clearing damaged or infected cells while limiting secondary inflammation. This may be particularly relevant to the proposed pro-resolving macrophage phenotype discussed later.
8.4. Integrated Role of Autophagy, Apoptosis, and Efferocytosis in AN-Acute
Under the present hypothesis, severe caloric restriction and persistent HyAc may increase reliance on complementary cellular maintenance and resolution mechanisms. Autophagy may conserve and recycle limited resources and support cellular survival; apoptosis may remove irreversibly damaged or infected cells; and efferocytosis may clear those cells while limiting inflammatory “spillover”. Together, these processes could help preserve tissue integrity and selected immune functions while reducing unnecessary inflammatory costs.
These adaptations also have limits. With prolonged severe starvation and continued activity, cellular injury may eventually exceed the capacity of these protective systems. Excessive cellular breakdown, widespread apoptosis, or inadequate efferocytosis could then contribute to tissue loss and secondary inflammation [89]. Thus, these mechanisms may initially support metabolic adaptation and immune resilience but become insufficient or maladaptive as metabolic depletion intensifies.
9. Acute-Phase Response
The acute-phase response (APR) is a coordinated systemic reaction to infection or tissue injury, involving inflammatory cytokines that stimulate the production of acute-phase proteins, fever, and characteristic behavioral changes such as fatigue and reduced activity [90]. These responses support host defense but also require substantial metabolic resources. In AN-acute, several components of the APR appear attenuated. The present model proposes that the absence of an APR may contribute to an inflammation-restrained host-defense strategy under conditions of severe energy restriction and persistent HyAc.
9.1. Acute-Phase Proteins in AN-Acute
During systemic inflammation, cytokines stimulate the liver to increase the production of acute-phase proteins that contribute to host defense, pathogen containment, tissue repair, and regulation of inflammation. C-reactive protein (CRP) is one of the best-known positive acute-phase proteins. Its hepatic synthesis is driven primarily by IL-6, with additional modulation by cytokines such as IL-1β and TNF-α [90].
Importantly, CRP does not appear elevated in AN. A recent systematic review and meta-analysis found significantly lower circulating CRP concentrations in individuals with AN than in HCs [91]. This is notable because circulating IL-6 has frequently been reported as elevated in AN-acute. The combination of elevated IL-6 with low CRP suggests that IL-6 elevation alone should not be interpreted as evidence of a coordinated systemic APR. One possibility proposed in the present model is that some circulating IL-6 reflects skeletal muscle release associated with HyAc rather than with conventional inflammatory activation. However, the source and signaling characteristics of IL-6 in AN-acute have not been directly established.
A similar lack of inflammation is suggested by the erythrocyte sedimentation rate (ESR), an indirect marker of inflammation that rises partly because of acute-phase proteins such as fibrinogen. In a study of 327 adolescent girls with eating disorders and weight loss, ESR values were within normal reference ranges [92]. These findings do not suggest prominent systemic inflammatory activation.
Taken together, low CRP and normal ESR argue against interpreting isolated cytokine elevations as evidence of generalized systemic inflammation in AN-acute. Instead, these findings are consistent with the inflammation-restrained phenotype proposed in this review.
9.2. Thermoregulatory Adaptation in AN-Acute
9.2.1. Fever as Part of the Acute-Phase Response
Fever is a major component of the APR. During infection, pyrogenic cytokines increase hypothalamic prostaglandin E2 signaling, raising the thermoregulatory set point. Fever-range temperatures can enhance leukocyte trafficking, selected innate effector functions, and several adaptive immune processes while restricting the growth of some pathogens [90,93].
However, fever is extremely metabolically expensive. Sustaining an elevated core temperature increases energy expenditure, which may be particularly difficult in AN-acute. Consistent with this, reduced febrile responses have been reported during bacterial infection in AN-acute [94]. This raises the possibility that some temperature-dependent immune effects may occur through other forms of warming rather than sustained cytokine-driven fever.
9.2.2. Activity-Induced Warming: Intermittent Fever-like Thermal Exposure
Physical activity provides one such source of warming. Skeletal-muscle contraction generates metabolic heat, and core temperature can rise during prolonged exercise in both HCs and AN-acute. Davies et al. [43] demonstrated that exercise could substantially increase core temperature in individuals with AN despite their characteristically low resting temperature. However, fever and exercise-induced hyperthermia arise through different mechanisms: fever raises the hypothalamic set point, whereas exercise increases heat production without resetting it. Nevertheless, once body temperature rises, immune cells may be exposed to similar thermal conditions.
Experimental studies show that fever-range temperatures can modify immune-cell trafficking and function [93], indicating that some temperature-dependent effects are mediated in part by the attained temperature and duration of exposure rather than solely by febrile signaling.
An evolutionary analogy is seen in ectotherms, which can develop “behavioral fever” by moving to warmer environments during infection. In infected desert iguanas, an increase of approximately 2 °C was associated with improved survival [95]. This does not imply that activity-induced warming in AN-acute is equivalent to behavioral fever, but it illustrates how modest increases in body temperature may support host defense.
Within the present model, persistent HyAc, including structured exercise and some forms of NEAT, could intermittently raise the characteristically low resting body temperature of AN-acute. These episodes would not constitute true fever but may provide intermittent fever-like thermal exposure with selected temperature-dependent immune effects. This possibility has not been directly tested.
9.2.3. Resting Low Core Temperature: Energy Conservation and Immune Restraint
At rest, individuals with AN-acute commonly exhibit reduced core temperature and marked cold intolerance, sometimes reaching clinically significant hypothermia [96,97]. This reflects starvation-related reductions in metabolic rate, heat production, and insulation.
Lower temperature can also restrain immune function. Mild experimental hypothermia reduces selected neutrophil antimicrobial functions, including reactive oxygen production and, in some studies, phagocytosis [98]. Its potential advantage may therefore lie less in pathogen clearance than in reducing metabolic demand and limiting inflammatory expenditure.
This distinction aligns with experimental work suggesting that fever and hypothermia may represent different host strategies. Fever can enhance antimicrobial defense but is energetically costly, whereas hypothermia may favor host preservation under severe metabolic constraint [99]. In rats with severe LPS- or Escherichia coli-induced inflammation, spontaneous hypothermia was associated with less organ dysfunction and improved survival despite a greater bacterial burden in the liver [100]. Thus, preservation of host function can occur without improved pathogen clearance.
Within the present hypothesis, resting hypothermia in AN-acute may therefore contribute to an energy-conserving, disease-tolerance phenotype, although this has not been directly demonstrated in AN.
9.2.4. Proposed Thermal Cycling in AN-Acute
The present model proposes two potentially complementary thermal states: a low resting temperature that conserves energy but may constrain selected immune functions, and activity-induced warming that may transiently support temperature-dependent immune processes. This alternation, or thermal cycling, may arise incidentally from severe energy restriction and a low core temperature, together with persistent HyAc, rather than from a specific immune adaptation.
Although movement, like the increase in metabolism associated with fever, is energetically costly, it serves functions beyond thermogenesis, including foraging and food-seeking [25], effects on mood and anxiety, and broader metabolic actions such as substrate mobilization and myokine signaling [101].
Thus, this proposed thermal pattern is consistent with energy conservation and possibly the selective preservation of innate defense. Whether this influences immune function in AN-acute remains to be tested.
9.3. Attenuated Sickness Behavior in AN-Acute
Sickness behavior is the coordinated behavioral component of the APR. In healthy individuals, inflammatory cytokines, particularly IL-1β, TNF-α, and IL-6, signal the brain and typically produce fatigue, sleepiness, reduced appetite and motivation, social withdrawal, and, importantly, a marked reduction in spontaneous activity. These responses encourage rest and redirect energy toward host defense and recovery [102].
The behavioral pattern observed in AN-acute is strikingly different. Casper et al. [19] found that after substantial weight loss, more than 80% of adolescents with restricting-AN reported an increased urge to move or physical or mental restlessness, and 95% reported at least one of these features. Thus, despite profound energy restriction, many individuals failed to show the characteristic sickness-behavior shift toward inactivity and rest. This contrasts sharply with semi-starved healthy individuals in the Minnesota study, who became progressively lethargic and increasingly avoided exertion as weight loss progressed [28,103].
Within the present hypothesis, persistent movement despite severe energy depletion may reflect attenuation or absence of the sickness-behavior component of the APR. This interpretation is consistent with reports that bacterial infections in AN can occur with reduced fever and few clinical signs or symptoms [104].
In AN-acute, IL-6 is frequently elevated, whereas IL-1β and TNF-α findings are more heterogeneous. Early meta-analytic work reported elevations in IL-6 and TNF-α, with less consistent results for IL-1β [7]. More recent evidence, however, found IL-6 to be reliably elevated in AN-acute, while TNF-α and IL-1β were similar to levels observed in healthy controls [69]. In the present model, a substantial portion of the elevation in IL-6 may reflect contraction-derived myokine IL-6 rather than immune-derived inflammatory IL-6. If so, an individual with AN-acute could develop an infection without mounting the usual symptoms of malaise, inactivity, or subjective illness. In this scenario, infection may be present yet remain relatively “silent” at the behavioral level.
Nutritional rehabilitation provides a further test of this hypothesis. As nutritional status improves and immune responsiveness recovers, the capacity to generate sickness behavior may also return [68]. This could help explain why some individuals report “feeling worse” during weight restoration, although this specific mechanism has not yet been directly demonstrated.
Overall, the persistence of movement despite profound energy restriction, together with reduced fever and muted clinical signs during documented infection, is consistent with attenuated sickness behavior in AN-acute. This remains a hypothesis, but it strengthens the broader possibility that infection in AN-acute may be expressed differently, rather than necessarily occurring less frequently.
9.4. Disease Tolerance in AN-Acute
The combined findings of reduced febrile responses, low resting temperature, restrained systemic inflammation, and potentially attenuated sickness behavior raise a broader question: whether AN-acute may rely more heavily on disease tolerance as a host-defense strategy.
Disease tolerance differs from pathogen resistance. Whereas resistance mechanisms act primarily to reduce pathogen burden, tolerance mechanisms limit the physiological and tissue damage caused by both pathogens and the host inflammatory response, thereby preserving host function without necessarily reducing pathogen load [105,106].
Within the present model, reduced febrile signaling, low resting temperature, restrained systemic inflammation, and constrained adaptive immune expansion may collectively be consistent with greater reliance on disease tolerance. Such a strategy could be particularly relevant under severe energy restriction, because inflammatory amplification, fever, and large adaptive responses themselves carry substantial metabolic and tissue costs.
Disease tolerance may also help explain reports of bacterial infection in AN-acute accompanied by remarkably limited fever or other clinical signs [104]. These observations do not establish disease tolerance in AN, but they are consistent with the possibility that preserving physiological function while limiting inflammatory costs becomes increasingly important when energy availability is severely constrained.
The question that follows is therefore not simply why systemic inflammatory responses appear muted, but how microbial challenges are managed when systemic inflammatory responses, including fever, acute-phase proteins, and sickness behavior, are restrained. This leads directly to the innate defenses considered next, particularly neutrophils, macrophages, and dendritic cells.
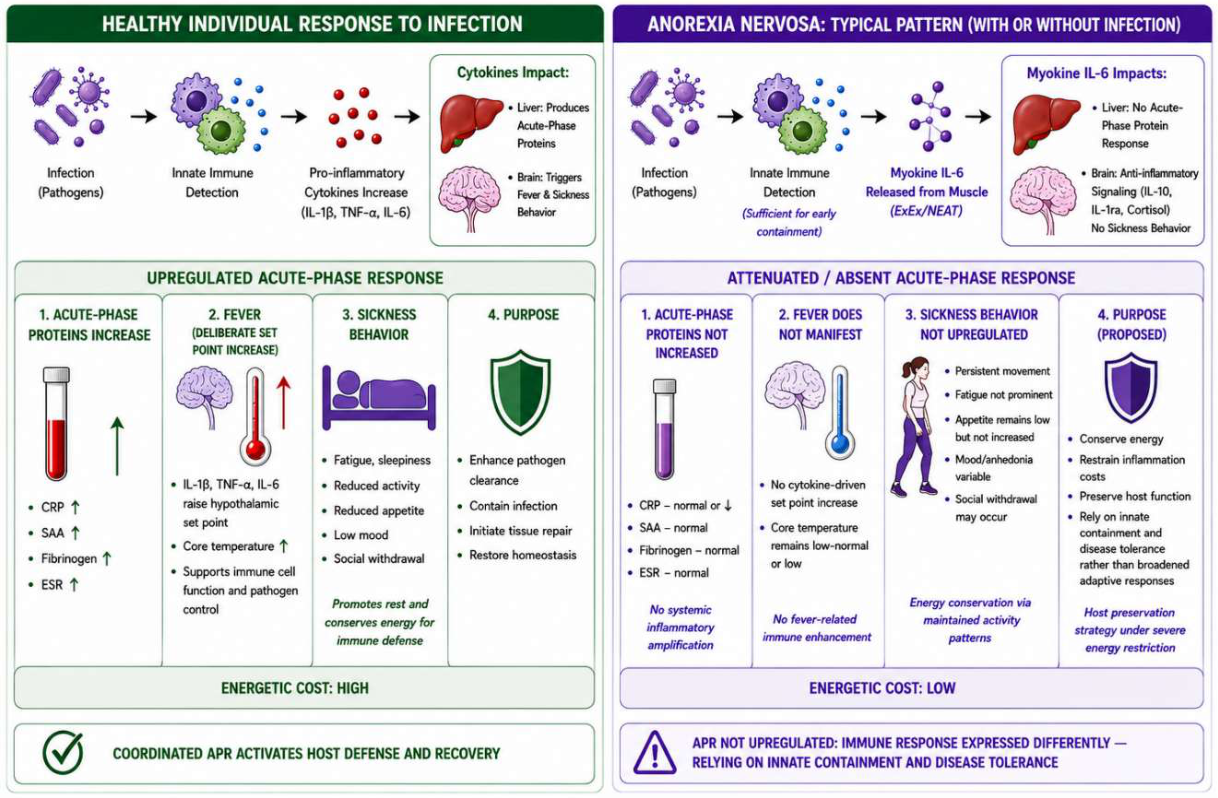
Figure 3.
Summary of the Acute Phase Response to infection in healthy individuals versus AN-acute.
10. Innate Immune Defenses in AN-Acute
Innate immunity provides a rapid, first-line defense against invading pathogens through cells such as neutrophils (PMNs), macrophages, dendritic cells (DCs), and natural killer (NK) cells, as well as soluble defenses such as cytokines and complement. These defenses recognize conserved microbial or damage signals and can often contain or eliminate pathogens before a substantial adaptive immune response is required.
When early containment is insufficient, innate immune cells, particularly DCs, help initiate the slower, antigen-specific adaptive immune response [107]. The present hypothesis proposes that this distinction may be particularly important in AN-acute: sufficient innate functions may remain available for early pathogen containment even when progression to a larger adaptive response is metabolically constrained.
10.1. Neutrophils: Front-Line Antimicrobial Defense in AN-Acute
Neutrophils are the most abundant circulating leukocytes among the first immune cells recruited during acute infection. Although they can cause collateral tissue damage, they also contribute to wound healing and inflammatory resolution. Contemporary research has reframed neutrophils from simple, destructive cells to highly adaptable participants in host defense. They eliminate microorganisms through phagocytosis, release of antimicrobial granules, production of reactive oxygen species (ROS), and formation of neutrophil extracellular traps (NETs). They also interact with macrophages, DCs, and other immune cells, contributing to pathogen clearance and to the regulation and resolution of inflammation [108].
Severe starvation can impair neutrophil biology without necessarily eliminating front-line innate defense. In AN, leukopenia and neutropenia are well recognized, particularly with greater nutritional severity, and bone-marrow hypoplasia or gelatinous transformation may further reduce neutrophil production and reserve [109]. Functional impairments have also been reported. Gotch et al. [110] demonstrated reduced granulocyte bactericidal activity in severely malnourished individuals with AN, with improvement following nutritional rehabilitation. Other studies describe abnormalities in selected neutrophil functions, although findings have been inconsistent [8]. Thus, starvation may reduce neutrophil numbers, reserves, and selected antimicrobial functions without necessarily producing a complete failure of front-line defense.
Neutrophils also have a metabolic profile that may be particularly relevant to AN-acute. They rely heavily on glycolysis for rapid energy production and possess intracellular glycogen stores that can be mobilized when extracellular fuel is limited. Experimental work indicates that glycogen synthesis and mobilization support neutrophil survival and bacterial killing under metabolically restricted conditions [111]. This metabolic flexibility could help sustain selected antimicrobial functions during nutrient limitation, although its importance has not been directly demonstrated in AN-acute.
Physical activity may further influence neutrophil availability. Acute exercise rapidly increases circulating neutrophil numbers through mobilization from vascular and bone-marrow pools, with stress hormones contributing to this response. Exercise can also transiently alter neutrophil functional activity, although these responses depend on exercise intensity, duration, and recovery [112].
In AN-acute, repeated bouts of activity or prolonged low-intensity movement could therefore repeatedly mobilize existing neutrophils into the circulation. The present hypothesis is not that HyAc makes neutrophils unusually effective, but that it may provide a partial “salvage” effect: starvation reduces neutrophil number and reserve, whereas repeated movement may temporarily increase the circulating availability of the remaining cells. Their predominantly glycolytic metabolism and ability to generate and mobilize intracellular glycogen may further help sustain rapid antimicrobial responses when extracellular fuel availability is limited [113].
Thus, PMNs may remain a critical component of rapid innate defense during severe energy restriction. Their numbers and some functions may be impaired, but metabolic flexibility together with repeated activity-related mobilization could help preserve sufficient front-line antimicrobial capacity for early pathogen containment. Whether this occurs in AN-acute remains hypothetical and requires direct study of neutrophil number, mobilization, antimicrobial function, and metabolism, ideally before and after controlled physical activity.
10.2. Macrophages: Pathogen Defense, Inflammatory Resolution, and Exercise
Macrophages are highly adaptable innate immune cells whose functions change in response to pathogens, metabolic conditions, and local cytokine signals. During acute infection, they can adopt more inflammatory functions and produce cytokines such as TNF-α, IL-1β, and IL-6, contributing to pathogen defense, the acute-phase response, fever, and sickness behavior [114]. As the threat is controlled, macrophage activity can shift toward resolution, including clearance of apoptotic cells through efferocytosis, restraint of excessive inflammation, and tissue repair [89,115]
Exercise can also influence macrophage function. Acute strenuous or tissue-damaging exercise may transiently increase inflammatory signaling, whereas repeated moderate activity is generally associated with a more inflammation-limiting systemic environment [35]. In experimental metabolic-tissue models, exercise training can reduce macrophage infiltration and shift the phenotype away from strongly inflammatory states toward more repair-oriented states [116]. These findings should not be interpreted as showing a universal M1-to-M2 transition across tissues, but they demonstrate that macrophage function is responsive to repeated physical activity.
This flexibility may be particularly relevant to AN-acute. Persistent physical activity occurs within a metabolic environment characterized by severe energy restriction, elevated cortisol and adiponectin, increased ketone availability, and repeated muscle-derived signaling. Glucocorticoids strongly restrain inflammatory gene expression and immune activation [75], while β-hydroxybutyrate can suppress NLRP3 inflammasome activation [83]. Adiponectin has also been associated with inflammation-limiting effects on macrophage signaling. Within the present hypothesis, these signals may collectively bias macrophage activity away from sustained inflammatory amplification and toward more pro-resolving functions.
Importantly, pro-resolving activity does not imply loss of antimicrobial capacity. Macrophage phenotypes exist along a continuum rather than as fixed M1 or M2 states [117]. Macrophages can therefore retain phagocytic and clearance functions while simultaneously limiting unnecessary inflammatory amplification and promoting resolution.
Thus, PMNs and macrophages may provide sufficient early containment at the innate level. Escalation to a substantial adaptive response, however, requires the activation and maturation of dendritic cells, followed by activation and expansion of antigen-specific T cells. This transition may represent a critical point of metabolic constraint in AN-acute.
10.3. Dendritic Cells: The Critical Bridge Between Innate and Adaptive Immunity
Dendritic cells (DCs) are specialized innate immune cells that continually survey tissues for microbes, foreign antigens, and signs of cellular damage. In their relatively immature or steady-state condition, they emphasize antigen sampling and local surveillance without necessarily initiating a strong adaptive response. Following appropriate activating signals, DCs mature, migrate to lymphoid tissues, and become highly effective antigen-presenting cells capable of initiating antigen-specific T-cell responses [118,119].
DCs are not normally reported as a distinct category on routine white blood cell counts. They are relatively uncommon in peripheral blood, while substantial populations reside in tissues and lymphoid organs [120]. Routine leukocyte counts in AN-acute therefore provide little information about DC abundance, activation state, or functional capacity.
10.3.1. From Surveillance to Activation: A Metabolic Transition
DC activation involves substantial metabolic reprogramming. Following recognition of sufficiently strong microbial or danger signals, DCs increase glycolysis and anabolic activity to support maturation, cytokine production, co-stimulatory molecule expression, migration, and effective T-cell stimulation [119,121].
This distinction may be particularly relevant to AN-acute. Neutrophils are highly glycolytic and can mobilize intracellular glycogen to support survival and antimicrobial function when extracellular substrates are limited [111]. DCs, by contrast, must make an additional metabolic investment when moving from relatively economical surveillance to an activated, immunogenic state.
Severe energy restriction could therefore make this transition more difficult when substrates and anabolic resources are limited. Under the present hypothesis, the problem may not be a failure of DCs to detect pathogens. Rather, the metabolic transition from surveillance to full immunogenic activation may be constrained. Severe energy restriction could raise the threshold for DC maturation and effective T-cell stimulation while permitting continued antigen sampling and innate surveillance. This mechanism has not been directly demonstrated in AN-acute.
10.3.2. Activation of CD4+ Helper T Cells: The Bridge to Adaptive Immunity
Following activation, mature DCs migrate to lymph nodes and provide the signals needed to activate naïve T cells. Productive T-cell activation requires antigen recognition through the T-cell receptor together with co-stimulatory signaling, while cytokines supplied by DCs and the surrounding inflammatory environment further determine the magnitude and differentiation of the response. These are commonly described as signals 1 (antigen recognition), 2 (co-stimulation), and 3 (cytokine instruction) [122,123].
Once activated, CD4+ T cells proliferate and coordinate multiple components of adaptive immunity, including B-cell antibody responses and effective CD8+ T-cell responses. This expansion is metabolically demanding. Naïve T cells are comparatively metabolically quiescent, whereas activation produces a marked increase in nutrient uptake, glycolysis, biosynthesis, and cellular growth to support differentiation and rapid clonal expansion [52].
The DC–CD4+ axis may therefore contain two sequential metabolic checkpoints in AN-acute. First, the DC must have sufficient metabolic resources to mature and provide effective antigen presentation, co-stimulation, and cytokine signaling. Second, the activated T cell must have sufficient resources to undertake the metabolic reprogramming and proliferation required for clonal expansion [52].
Severe energy restriction could constrain either checkpoint without eliminating the lymphocytes already present. Naïve and memory T cells can persist in comparatively quiescent metabolic states, whereas activation and rapid expansion require substantially greater nutrient and biosynthetic support [52]. The presence of circulating adaptive immune cells in AN-acute therefore does not establish that their capacity for full activation and expansion is preserved.
10.3.3. What Is Known About DCs in AN-Acute?
Direct evidence regarding DC function in AN is limited. Pászthy et al. [67] examined circulating myeloid and plasmacytoid DC populations together with regulatory T cells and other lymphocyte populations and did not demonstrate a generalized loss of circulating DCs. Thus, available data do not suggest that DCs are simply absent in AN-acute.
Related work from the same group reported altered lymphocyte activation responses, including delayed intracellular calcium signaling and a lower proportion of IL-2-positive CD4+ cells following stimulation. These findings illustrate that preserved cell numbers do not necessarily imply preserved activation capacity. Broader reviews similarly describe heterogeneous findings in lymphocyte populations and function and emphasize the limited information available regarding DC function in AN [8].
Importantly, existing studies have not directly tested the complete sequence proposed here: DC metabolic activation → maturation and migration → effective co-stimulation → CD4+ T-cell activation → clonal expansion.
The present hypothesis is therefore not that DCs or lymphocytes are absent or globally defective in AN-acute. Rather, severe metabolic constraint may permit continued DC surveillance while limiting the transition to full immunogenic activation and subsequent CD4+ expansion. This proposed DC–CD4+ metabolic bottleneck could restrict adaptive upregulation while leaving substantial innate defense available. Whether such a bottleneck occurs in AN-acute remains unknown and represents an important testable prediction of the present model.
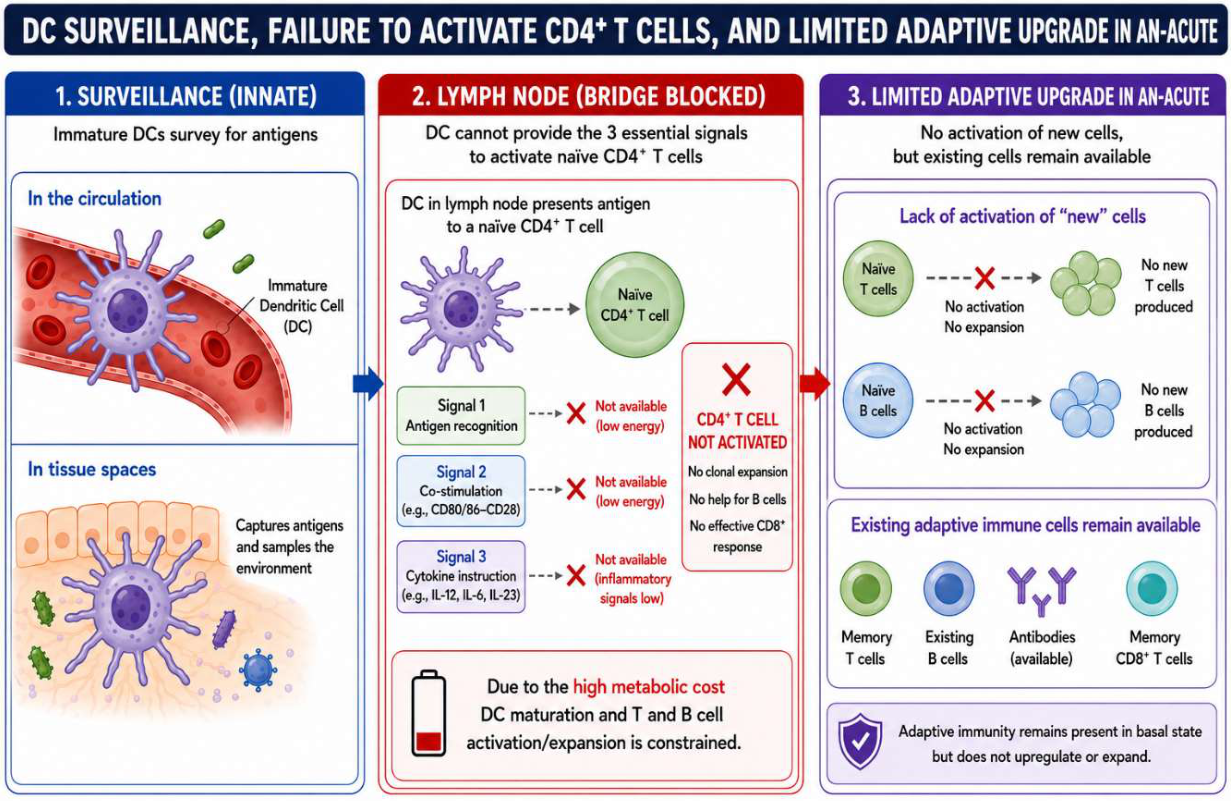
Figure 4.
Proposed DC–CD4+ metabolic bottleneck in AN-acute, allowing continued dendritic-cell surveillance while constraining CD4+ T-cell activation and adaptive immune expansion.
Figure 4.
Proposed DC–CD4+ metabolic bottleneck in AN-acute, allowing continued dendritic-cell surveillance while constraining CD4+ T-cell activation and adaptive immune expansion.
11. Summary of the Proposed Immune Hypothesis (Figure 5)
The present model proposes that the immune phenotype of AN-acute reflects not generalized immune failure, but a selective reorganization of host defense under severe and prolonged energy constraint. Persistent energy restriction, compounded by HyAc, may reduce leptin signaling, increase AMPK activity, and suppress mTORC1-dependent anabolic processes, favoring cellular survival and energy conservation while making metabolically expensive adaptive immune activation more difficult.
Within this environment, muscle-derived IL-6 generated during repeated activity, together with elevated cortisol, adiponectin, and ketone bodies, may promote fuel mobilization while restraining excessive inflammatory amplification. These signals may also support cellular maintenance and resolution processes, including autophagy and, potentially, apoptosis followed by efferocytosis. The resulting immune environment may therefore favor preservation, repair, and controlled inflammation rather than maximal systemic activation.
This restraint may extend to the acute-phase response. Reduced acute-phase proteins, attenuated fever, low resting temperature, and diminished sickness behavior could lower the energetic and tissue costs of infection and make some infections less clinically apparent.
At the same time, selected innate defenses may remain comparatively resilient. Neutrophils are strongly glycolytic and can mobilize intracellular glycogen, while macrophages can combine antimicrobial clearance with pro-resolving functions. Persistent HyAc may further mobilize innate cells and provide repeated autonomic, myokine, and thermal signals. Thus, PMNs and macrophages may retain sufficient capacity for early pathogen containment despite restrained systemic inflammation.
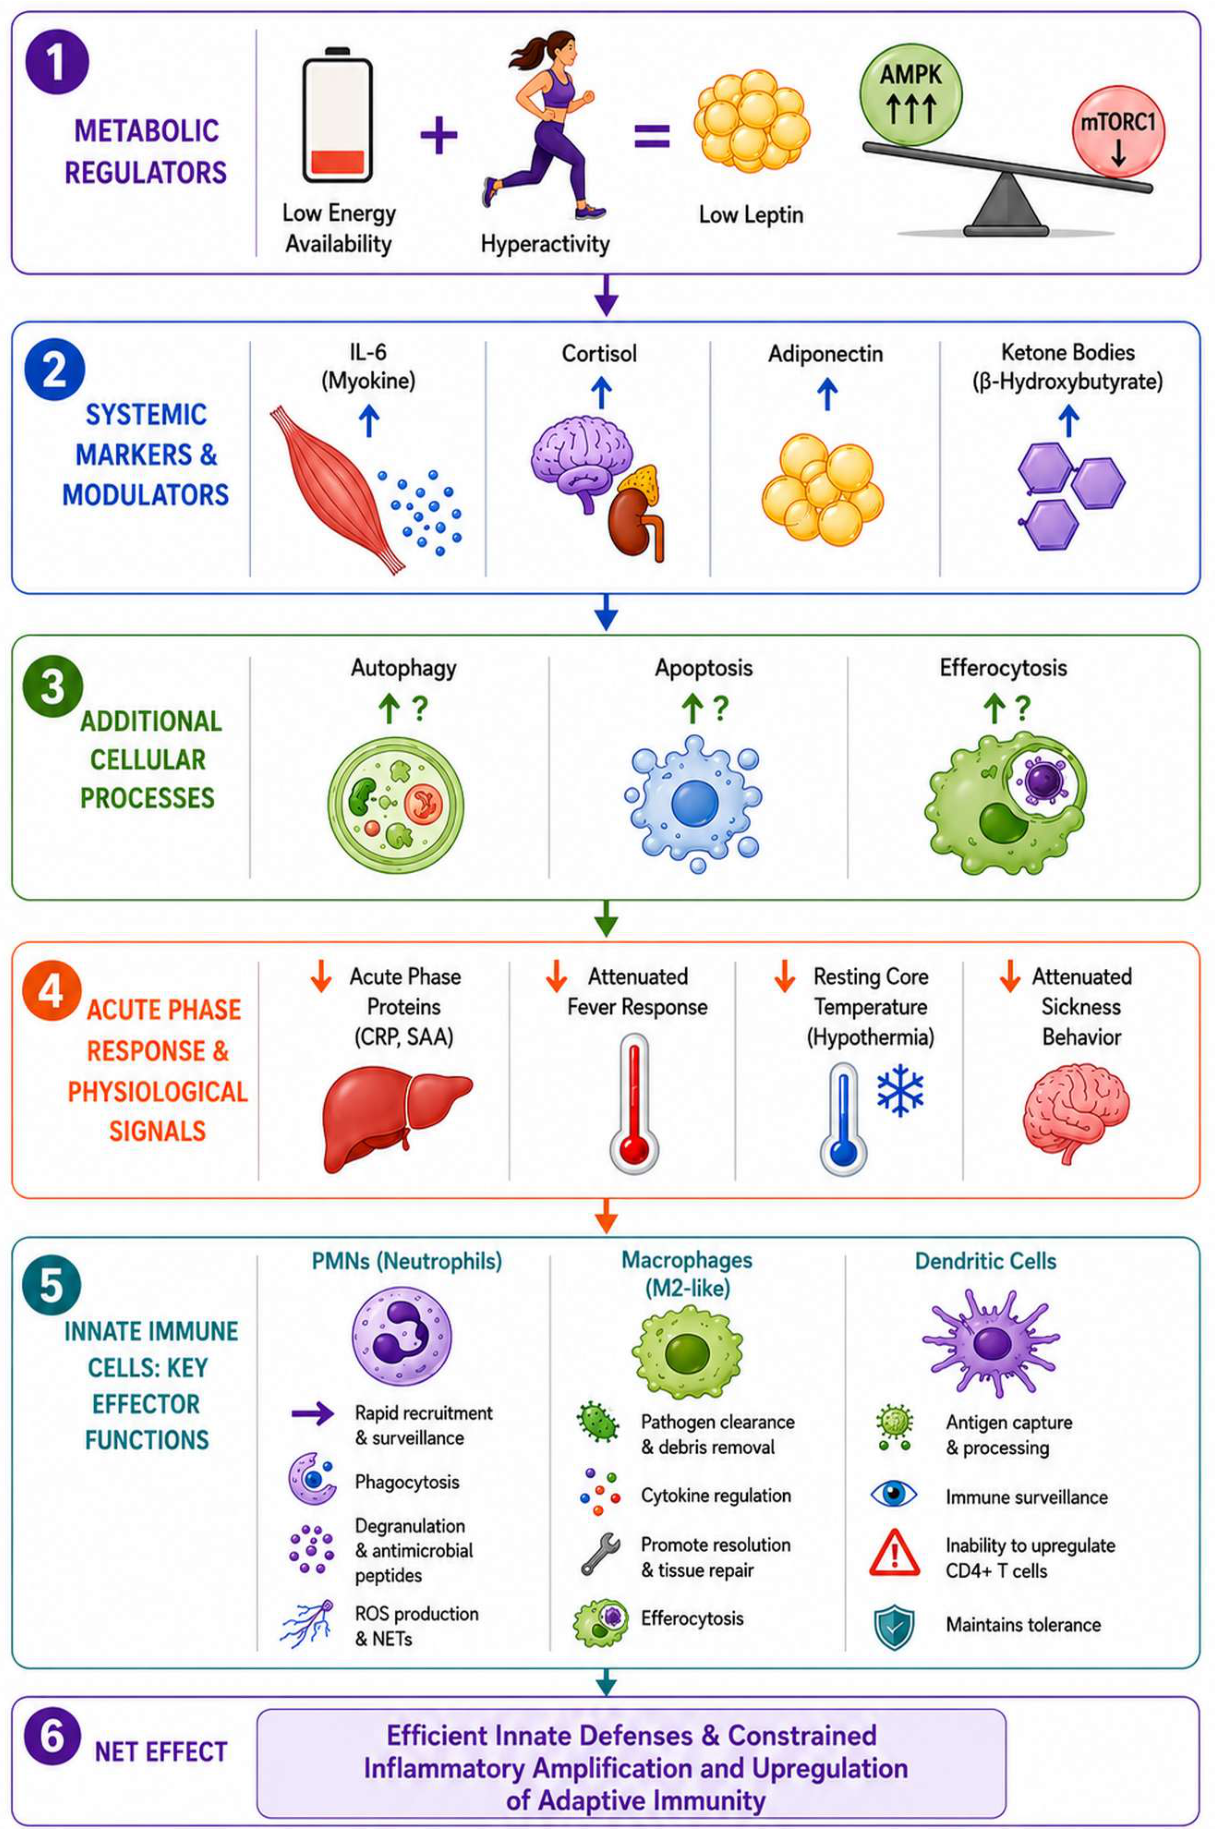
Figure 5.
Summary of the proposed hypothesis illustrating how low caloric intake combined with hyperactivity (HyAc) may influence immune defense in AN-acute.
Figure 5.
Summary of the proposed hypothesis illustrating how low caloric intake combined with hyperactivity (HyAc) may influence immune defense in AN-acute.
The principal metabolic bottleneck may occur at the transition from innate to adaptive immunity. DCs may continue antigen surveillance, while full maturation, migration, co-stimulation, and subsequent CD4+ T-cell activation require substantial metabolic reprogramming. A second constraint may occur during T-cell clonal expansion, which requires increased nutrient uptake, glycolysis, biosynthesis, and mTORC1-dependent growth. The proposed result is a DC–CD4 metabolic bottleneck that limits adaptive escalation without eliminating the adaptive immune cells already present.
Taken together, the model predicts energy conservation, selective preservation of innate containment, restrained inflammatory amplification, and constrained adaptive upregulation. Some microbial challenges may be contained early; others may remain relatively “silent” because fever, acute-phase responses, and sickness behavior are attenuated; and, in some circumstances, host protection may rely more heavily on disease tolerance than on complete pathogen elimination.
This hypothesis does not propose that AN-acute confers superior immunity. Rather, under extreme metabolic constraint, the immune system may prioritize functions immediately necessary for survival while limiting prolonged, energetically costly, or tissue-damaging responses. Persistent HyAc may be an important modifier of this state. The model is testable through measures of neutrophil and macrophage function, DC–CD4 activation, acute-phase responses, and changes in response to nutritional restoration and controlled physical activity.
12. Testable Predictions
The present hypothesis can be tested by comparing immune and physiological responses in AN-acute with those of healthy controls and by following patients during nutritional recovery.
First, studies should determine whether low-intensity movement produces a meaningful physiological response in AN-acute. Continuous monitoring of activity, heart rate, HRV, and temperature, together with blood measurements before and after a standardized walking task, could show whether mild movement produces repeated exercise-like effects.
Second, the model predicts that innate immune defenses are relatively preserved, particularly neutrophil and macrophage functions involved in early pathogen containment and inflammatory resolution.
Third, the proposed dendritic-cell–CD4+ bottleneck should be tested directly. The key question is whether dendritic cells can maintain basic immune surveillance while having greater difficulty fully activating and stimulating CD4+ T cells during severe energy restriction.
Finally, studies should examine whether adaptive immune responses and the acute-phase response strengthen with nutritional restoration, using measures such as vaccine responses, delayed-type hypersensitivity, fever, inflammatory markers, and sickness behavior.
Together, these studies could determine whether AN-acute is characterized by generalized immune impairment or, as proposed here, by preserved innate containment, restrained systemic inflammation, and constrained adaptive upregulation.
13. Conclusion
The apparent immune paradox in AN-acute is that, despite profound undernutrition and reported immune abnormalities, individuals have historically been described as experiencing fewer clinically apparent infections than might be expected [12,13]. The present model treats this not as a true paradox but as an unresolved clinical observation: it remains unclear whether infections are genuinely less frequent or whether microbial challenges are contained or clinically expressed differently under conditions of severe energy restriction and persistent HyAc.
In summary, the immune phenotype proposed for AN-acute reflects a shift toward energy conservation, preserved innate containment, restrained inflammatory amplification, and constrained adaptive upregulation. Some infections may be contained early; others may present with muted clinical signs; and, in some circumstances, host protection may rely more heavily on disease tolerance.
The central question, therefore, may not be whether individuals with AN-acute experience fewer infections, but how microbial challenges are managed and clinically expressed when extreme energy restriction and sustained physical activity shape the organization of immune defense.
Author Contributions
The author confirms being the sole contributor of this work and has approved it for publication.
Funding
No funding was received.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study.
Use of Artificial Intelligence
During preparation of this manuscript, the author used ChatGPT (OpenAI) and Copilot (Microsoft) to improve the grammar, clarity, readability, and organization of the author’s draft text and, in part, to help identify literature for independent verification. The author developed the conceptual framework, scientific interpretations, hypotheses, and conclusions. The author reviewed, revised, and independently verified all AI-assisted text, factual statements, and references and takes full responsibility for the final manuscript. ChatGPT generated all diagrams and Tables.
Acknowledgments
For editorial assistance: Dr. Michael Stone, Professor Emeritus, East Tennessee State University, Tennessee, USA, and Institute for Sport, Physical Education, and Health Science, University of Edinburgh, Scotland.
Conflicts of Interest
There are no conflicts of interest.
References
- Treasure, J.; Willmott, D.; Ambwani, S.; Cardi, V.; Clark Bryan, D.; Rowlands, K.; et al. Cognitive Interpersonal Model for Anorexia Nervosa Revisited: The Perpetuating Factors that Contribute to the Development of the Severe and Enduring Illness. J. Clin. Med. 2020, 9(3), 630. [Google Scholar] [CrossRef] [PubMed]
- Zipfel, S.; Giel, K.E.; Bulik, C.M.; Hay, P.; Schmidt, U. Anorexia nervosa: aetiology, assessment, and treatment. Lancet Psychiatry 2015, 2(12), 1099–1111. [Google Scholar] [CrossRef] [PubMed]
- Misra, M.; Klibanski, A. Endocrine consequences of anorexia nervosa. Lancet Diabetes Endocrinol. 2014, 2(7), 581–592. [Google Scholar] [CrossRef] [PubMed]
- Muller, T.D.; Nogueiras, R.; Andermann, M.L.; Andrews, Z.B.; Anker, S.D.; Argente, J.; et al. Ghrelin. Mol. Metab. 2015, 4(6), 437–460. [Google Scholar] [CrossRef] [PubMed]
- Keys, A.; Henschel, A.; Brožek, J. The biology of human starvation Volume II, 1st ed.; University of Minnesota Press: Place of publication not identified, 1950. [Google Scholar]
- Nova, E.; Marcos, A. Immunocompetence to assess nutritional status in eating disorders. Expert Rev. Clin. Immunol. 2(3), 433–444. [CrossRef] [PubMed]
- Solmi, M.; Veronese, N.; Favaro, A.; Santonastaso, P.; Manzato, E.; Sergi, G.; et al. Inflammatory cytokines and anorexia nervosa: A meta-analysis of cross-sectional and longitudinal studies. Psychoneuroendocrinology 2015, 51, 237–252. [Google Scholar] [CrossRef] [PubMed]
- Gibson, D.; Mehler, P.S. Anorexia Nervosa and the Immune System-A Narrative Review. J. Clin. Med. 2019, 8(11), 1915. [Google Scholar] [CrossRef] [PubMed]
- Chandra, R.K. Nutrition and the immune system: an introduction. Am. J. Clin. Nutr. 1997, 66(2), 460S–463S. [Google Scholar] [CrossRef] [PubMed]
- Calder, P.C.; Jackson, A.A. Undernutrition, infection and immune function. Nutr. Res. Rev. 2000, 13(1), 3–29. [Google Scholar] [CrossRef] [PubMed]
- Armstrong-Esther, C.A.; Lacey, J.H.; Crisp, A.H.; Bryant, T.N. An investigation of the immune response of patients suffering from anorexia nervosa. Postgrad. Med. J. 1978, 54(632), 395–399. [Google Scholar] [CrossRef] [PubMed]
- Bowers, T.K.; Eckert, E. Leukopenia in anorexia nervosa. Lack of increased risk of infection. Arch. Intern Med. 1978, 138(10), 1520–1523. [Google Scholar] [CrossRef]
- Brown, R.F.; Bartrop, R.; Birmingham, C.L. Immunological disturbance and infectious disease in anorexia nervosa: a review. Acta Neuropsychiatr. 2008, 20(3), 117–128. [Google Scholar] [CrossRef] [PubMed]
- Campbell, J.P.; Turner, J.E. Debunking the Myth of Exercise-Induced Immune Suppression: Redefining the Impact of Exercise on Immunological Health Across the Lifespan. Front Immunol. 2018, 9, 648. [Google Scholar] [CrossRef] [PubMed]
- Treasure, J.; Russell, G. The case for early intervention in anorexia nervosa: theoretical exploration of maintaining factors. Br. J. Psychiatry 2011, 199(1), 5–7. [Google Scholar] [CrossRef] [PubMed]
- Machado, R.B.; Rocha, M.R.; Suchecki, D. Brain prolactin is involved in stress-induced REM sleep rebound. Horm. Behav. 2017, 89, 38–47. [Google Scholar] [CrossRef] [PubMed]
- Fernstrom, M.H.; Weltzin, T.E.; Neuberger, S.; Srinivasagam, N.; Kaye, W.H. Twenty-four-hour food intake in patients with anorexia nervosa and in healthy control subjects. Biol. Psychiatry 1994, 36(10), 696–702. [Google Scholar] [CrossRef] [PubMed]
- Germain, N.; Genteuil, C.D.; Belleton, G.; Da Silva, T.L.; Exbrayat, C.; Degas, F.; et al. Continuous glucose monitoring assessment in patients suffering from anorexia nervosa reveals chronic prolonged mild hypoglycemia all over the nycthemeron. Eur. Eat. Disord. Rev. 2023, 31(3), 402–412. [Google Scholar] [CrossRef] [PubMed]
- Casper, R.C. Might Starvation-Induced Adaptations in Muscle Mass, Muscle Morphology and Muscle Function Contribute to the Increased Urge for Movement and to Spontaneous Physical Activity in Anorexia Nervosa? Nutrients 2020, 12(7). [Google Scholar] [CrossRef] [PubMed]
- Gull, W.W. Anorexia nervosa (apepsia hysterica, anorexia hysterica). 1868. Obes. Res. 1997, 5(5), 498–502. [Google Scholar] [CrossRef] [PubMed]
- Crisp, A.H. The possible significance of some behavioural correlates of weight and carbohydrate intake. J. Psychosom. Res. 1967, 11(1), 117–131. [Google Scholar] [CrossRef] [PubMed]
- Meyer, C.; Taranis, L.; Goodwin, H.; Haycraft, E. Compulsive exercise and eating disorders. Eur. Eat. Disord. Rev. 2011, 19(3), 174–189. [Google Scholar] [CrossRef] [PubMed]
- Touyz, S.; Hay, P.; Noetel, M. Is the neglect of exercise in anorexia nervosa research a case of “running out” of ideas or do we need to take a “LEAP” of faith into the future? J. Eat. Disord. eCollection 2017. 2017, 5, 35–z. [Google Scholar] [CrossRef] [PubMed]
- Young, S.; Touyz, S.; Meyer, C.; Arcelus, J.; Rhodes, P.; Madden, S.; et al. Validity of Exercise Measures in Adults with Anorexia Nervosa: The EDE, Compulsive Exercise Test and Other Self-Report Scales. Int. J. Eat. Disord. 2017, 50(5), 533–541. [Google Scholar] [CrossRef] [PubMed]
- Guisinger, S. Adapted to flee famine: adding an evolutionary perspective on anorexia nervosa. Psychol. Rev. 2003, 110(4), 745–761. [Google Scholar] [CrossRef] [PubMed]
- Gutierrez, E.; Vazquez, R.; Boakes, R.A. Activity-based anorexia: ambient temperature has been a neglected factor. Psychon. Bull. Rev. 2002, 9(2), 239–249. [Google Scholar] [CrossRef] [PubMed]
- Scolnick, B.; Zupec-Kania, B.; Calabrese, L.; Aoki, C.; Hildebrandt, T. Remission from Chronic Anorexia Nervosa With Ketogenic Diet and Ketamine: Case Report. Front Psychiatry 2020, 11, 763. [Google Scholar] [CrossRef] [PubMed]
- Smith, L.L. Similarities and differences regarding acute anorexia nervosa and semi-starvation: does behavioral thermoregulation play a central role? Front Behav. Neurosci. 2023, 17, 1243572. [Google Scholar] [CrossRef] [PubMed]
- O’Neill, L.A.J.; Pearce, E.J. Immunometabolism governs dendritic cell and macrophage function. J. Exp. Med. 2016, 213(1), 15–23. [Google Scholar] [CrossRef] [PubMed]
- Buck, M.D.; Sowell, R.T.; Kaech, S.M.; Pearce, E.L. Metabolic Instruction of Immunity. Cell 2017, 169(4), 570–586. [Google Scholar] [CrossRef] [PubMed]
- McDade, T.W. Life history theory and the immune system: steps toward a human ecological immunology. Am. J. Phys. Anthropol. 2003, Suppl 37, 100–125. [Google Scholar] [CrossRef] [PubMed]
- Rauw, W.M. Immune response from a resource allocation perspective. Front Genet 2012, 3, 267. [Google Scholar] [CrossRef] [PubMed]
- Casper, R.C. The ‘drive for activity’ and “restlessness” in anorexia nervosa: potential pathways. J. Affect Disord. 2006, 92(1), 99–107. [Google Scholar] [CrossRef] [PubMed]
- Casper, R.C. Restless activation and drive for activity in anorexia nervosa may reflect a disorder of energy homeostasis. Int. J. Eat. Disord. 2016, 49(8), 750–752. [Google Scholar] [CrossRef] [PubMed]
- Gleeson, M.; Bishop, N.C.; Stensel, D.J.; Lindley, M.R.; Mastana, S.S.; Nimmo, M.A. The anti-inflammatory effects of exercise: mechanisms and implications for the prevention and treatment of disease. Nat. Rev. Immunol. 2011, 11(9), 607–615. [Google Scholar] [CrossRef] [PubMed]
- Smith, L.L. The Central Role of Hypothermia and Hyperactivity in Anorexia Nervosa: A Hypothesis. Front Behav. Neurosci. 2021, 15, 700645. [Google Scholar] [CrossRef] [PubMed]
- Levine, J.A.; Kotz, C.M. NEAT--non-exercise activity thermogenesis--egocentric & geocentric environmental factors vs. biological regulation. Acta Physiol. Scand. 2005, 184(4), 309–318. [Google Scholar] [CrossRef] [PubMed]
- Belak, L.; Gianini, L.; Klein, D.A.; Sazonov, E.; Keegan, K.; Neustadt, E.; et al. Measurement of fidgeting in patients with anorexia nervosa using a novel shoe-based monitor. Eat. Behav. 2017, 24, 45–48. [Google Scholar] [CrossRef] [PubMed]
- Petretta, M.; Bonaduce, D.; Scalfi, L.; de Filippo, E.; Marciano, F.; Migaux, M.L.; et al. Heart rate variability as a measure of autonomic nervous system function in anorexia nervosa. Clin. Cardiol. 1997, 20(3), 219–224. [Google Scholar] [CrossRef] [PubMed]
- Peyser, D.; Scolnick, B.; Hildebrandt, T.; Taylor, J.A. Heart rate variability as a biomarker for anorexia nervosa: A review. Eur. Eat. Disord. Rev. 2021, 29(1), 20–31. [Google Scholar] [CrossRef] [PubMed]
- Billeci, L.; Tonacci, A.; Brunori, E.; Raso, R.; Calderoni, S.; Maestro, S.; et al. Autonomic Nervous System Response during Light Physical Activity in Adolescents with Anorexia Nervosa Measured by Wearable Devices. Sensors 2019, 19(12), 2820. [Google Scholar] [CrossRef] [PubMed]
- Kolnes, L. ‘Feelings stronger than reason’: conflicting experiences of exercise in women with anorexia nervosa. J. Eat. Disord. 2016, 4, 6–8. [Google Scholar]
- Davies, C.T.; Fohlin, L.; Thoren, C. Temperature regulation in anorexia nervosa patients during prolonged exercise. Acta Med. Scand. 1979, 205(4), 257–262. [Google Scholar] [CrossRef] [PubMed]
- Gleeson, M. Immune function in sport and exercise. J. Appl. Physiol. (1985) 2007, 103(2), 693–699. [Google Scholar] [CrossRef] [PubMed]
- Nieman, D.C.; Wentz, L.M. The compelling link between physical activity and the body’s defense system. J. Sport Health Sci. 2019, 8(3), 201–217. [Google Scholar] [CrossRef] [PubMed]
- Medzhitov, R. Recognition of microorganisms and activation of the immune response. Nature 2007, 449(7164), 819–826. [Google Scholar] [CrossRef] [PubMed]
- Flajnik, M.F.; Kasahara, M. Origin and evolution of the adaptive immune system: genetic events and selective pressures. Nat. Rev. Genet 2010, 11(1), 47–59. [Google Scholar] [CrossRef] [PubMed]
- Medzhitov, R. Innate immunity: quo vadis? Nat. Immunol. 2010, 11(7), 551–553. [Google Scholar] [CrossRef] [PubMed]
- Bonilla, F.A.; Oettgen, H.C. Adaptive immunity. J. Allergy Clin. Immunol. 2010, 125((2) Suppl 2, 33. [Google Scholar] [CrossRef]
- Heinzel, S.; Marchingo, J.M.; Horton, M.B.; Hodgkin, P.D. The regulation of lymphocyte activation and proliferation. Curr. Opin. Immunol. 2018, 51, 32–38. [Google Scholar] [CrossRef] [PubMed]
- Liu, J.; Zhang, X.; Cheng, Y.; Cao, X. Dendritic cell migration in inflammation and immunity. Cell Mol. Immunol. 2021, 18(11), 2461–2471. [Google Scholar] [CrossRef] [PubMed]
- Chapman, N.M.; Boothby, M.R.; Chi, H. Metabolic coordination of T cell quiescence and activation. Nat. Rev. Immunol. 2020, 20(1), 55–70. [Google Scholar] [CrossRef] [PubMed]
- Hebebrand, J.; Blum, W.F.; Barth, N.; Coners, H.; Englaro, P.; Juul, A.; et al. Leptin levels in patients with anorexia nervosa are reduced in the acute stage and elevated upon short-term weight restoration. Mol. Psychiatry 1997, 2(4), 330–334. [Google Scholar] [CrossRef] [PubMed]
- Misra, M.; Miller, K.K.; Almazan, C.; Ramaswamy, K.; Aggarwal, A.; Herzog, D.B.; et al. Hormonal and body composition predictors of soluble leptin receptor, leptin, and free leptin index in adolescent girls with anorexia nervosa and controls and relation to insulin sensitivity. J. Clin. Endocrinol. Metab. 2004, 89(7), 3486–3495. [Google Scholar] [CrossRef] [PubMed]
- Misra, M.; Klibanski, A. Endocrine consequences of anorexia nervosa. Lancet Diabetes Endocrinol. 2014, 2(7), 581–592. [Google Scholar] [CrossRef] [PubMed]
- Lord, G.M.; Matarese, G.; Howard, J.K.; Baker, R.J.; Bloom, S.R.; Lechler, R.I. Leptin modulates the T-cell immune response and reverses starvation-induced immunosuppression. Nature 1998, 394(6696), 897–901. [Google Scholar] [CrossRef] [PubMed]
- Saucillo, D.C.; Gerriets, V.A.; Sheng, J.; Rathmell, J.C.; Maciver, N.J. Leptin metabolically licenses T cells for activation to link nutrition and immunity. J. Immunol. 2014, 192(1), 136–144. [Google Scholar] [CrossRef] [PubMed]
- Naylor, C.; Petri, W.A.J. Leptin Regulation of Immune Responses. Trends Mol. Med. 2016, 22(2), 88–98. [Google Scholar] [CrossRef] [PubMed]
- Hardie, D.G.; Ross, F.A.; Hawley, S.A. AMPK: a nutrient and energy sensor that maintains energy homeostasis. Nat. Rev. Mol. Cell Biol. 2012, 13(4), 251–262. [Google Scholar] [CrossRef] [PubMed]
- Herzig, S.; Shaw, R.J. AMPK: guardian of metabolism and mitochondrial homeostasis. Nat. Rev. Mol. Cell Biol. 2018, 19(2), 121–135. [Google Scholar] [CrossRef] [PubMed]
- Gwinn, D.M.; Shackelford, D.B.; Egan, D.F.; Mihaylova, M.M.; Mery, A.; Vasquez, D.S.; et al. AMPK phosphorylation of raptor mediates a metabolic checkpoint. Mol. Cell 2008, 30(2), 214–226. [Google Scholar] [CrossRef] [PubMed]
- Blagih, J.; Coulombe, F.; Vincent, E.E.; Dupuy, F.; Galicia-Vazquez, G.; Yurchenko, E.; et al. The energy sensor AMPK regulates T cell metabolic adaptation and effector responses in vivo. Immunity 2015, 42(1), 41–54. [Google Scholar] [CrossRef] [PubMed]
- O’Neill, L.A.J.; Kishton, R.J.; Rathmell, J. A guide to immunometabolism for immunologists. Nat. Rev. Immunol. 16(9), 553–565. [CrossRef] [PubMed]
- Saxton, R.A.; Sabatini, D.M. mTOR Signaling in Growth, Metabolism, and Disease. Cell 2017, 168(6), 960–976. [Google Scholar] [CrossRef] [PubMed]
- Procaccini, C.; De Rosa, V.; Galgani, M.; Carbone, F.; Cassano, S.; Greco, D.; et al. Leptin-induced mTOR activation defines a specific molecular and transcriptional signature controlling CD4+ effector T cell responses. J. Immunol. 2012, 189(6), 2941–2953. [Google Scholar] [CrossRef] [PubMed]
- O’Neill, L.A.J.; Hardie, D.G. Metabolism of inflammation limited by AMPK and pseudo-starvation. Nature 2013, 493(7432), 346–355. [Google Scholar] [CrossRef] [PubMed]
- Paszthy, B.; Svec, P.; Vasarhelyi, B.; Tury, F.; Mazzag, J.; Tulassay, T.; et al. Investigation of regulatory T cells in anorexia nervosa. Eur. J. Clin. Nutr. 2007, 61(11), 1245–1249. [Google Scholar] [CrossRef] [PubMed]
- Nagata, T.; Kiriike, N.; Tobitani, W.; Kawarada, Y.; Matsunaga, H.; Yamagami, S. Lymphocyte subset, lymphocyte proliferative response, and soluble interleukin-2 receptor in anorexic patients. Biol. Psychiatry 1999, 45(4), 471–474. [Google Scholar] [CrossRef] [PubMed]
- Keeler, J.L.; Bovenberg, C.; Himmerich, H.; Treasure, J.; Carter, B.; Schmidt, U.; et al. Cytokine concentrations in people with eating disorders: A comprehensive updated systematic review and meta-analysis. Commun. Med. (Lond) 2025, 5(1), 408–z. [Google Scholar] [CrossRef] [PubMed]
- Pedersen, B.K.; Febbraio, M.A. Muscle as an endocrine organ: focus on muscle-derived interleukin-6. Physiol. Rev. 2008, 88(4), 1379–1406. [Google Scholar] [CrossRef] [PubMed]
- Rose-John, S.; Jenkins, B.J.; Garbers, C.; Moll, J.M.; Scheller, J. Targeting IL-6 trans-signalling: past, present and future prospects. Nat. Rev. Immunol. 2023, 23(10), 666–681. [Google Scholar] [CrossRef] [PubMed]
- Carey, A.L.; Steinberg, G.R.; Macaulay, S.L.; Thomas, W.G.; Holmes, A.G.; Ramm, G.; et al. Interleukin-6 increases insulin-stimulated glucose disposal in humans and glucose uptake and fatty acid oxidation in vitro via AMP-activated protein kinase. Diabetes 2006, 55(10), 2688–2697. [Google Scholar] [CrossRef] [PubMed]
- Thavaraputta, S.; Ungprasert, P.; Witchel, S.F.; Fazeli, P.K. Anorexia nervosa and adrenal hormones: a systematic review and meta-analysis. Eur. J. Endocrinol. 2023, 189(3), S64–S73. [Google Scholar] [CrossRef] [PubMed]
- Hackney, A.C. Exercise as a stressor to the human neuroendocrine system. Medicina 2006, 42(10), 788–797. [Google Scholar] [PubMed]
- Cain, D.W.; Cidlowski, J.A. Immune regulation by glucocorticoids. Nat. Rev. Immunol. 2017, 17(4), 233–247. [Google Scholar] [CrossRef] [PubMed]
- Kuo, T.; Harris, C.A.; Wang, J. Metabolic functions of glucocorticoid receptor in skeletal muscle. Mol. Cell Endocrinol. 2013, 380(1-2), 79–88. [Google Scholar] [CrossRef] [PubMed]
- Kuo, T.; McQueen, A.; Chen, T.; Wang, J. Regulation of Glucose Homeostasis by Glucocorticoids. Adv. Exp. Med. Biol. 2015, 872, 99–126. [Google Scholar] [CrossRef] [PubMed]
- Pannacciulli, N.; Vettor, R.; Milan, G.; Granzotto, M.; Catucci, A.; Federspil, G.; et al. Anorexia nervosa is characterized by increased adiponectin plasma levels and reduced nonoxidative glucose metabolism. J. Clin. Endocrinol. Metab. 2003, 88(4), 1748–1752. [Google Scholar] [CrossRef] [PubMed]
- Yamauchi, T.; Kamon, J.; Minokoshi, Y.; Ito, Y.; Waki, H.; Uchida, S.; et al. Adiponectin stimulates glucose utilization and fatty-acid oxidation by activating AMP-activated protein kinase. Nat. Med. 2002, 8(11), 1288–1295. [Google Scholar] [CrossRef] [PubMed]
- Kadowaki, T.; Yamauchi, T. Adiponectin and adiponectin receptors. Endocr. Rev. 2005, 26(3), 439–451. [Google Scholar] [CrossRef] [PubMed]
- Luo, Y.; Liu, M. Adiponectin: a versatile player of innate immunity. J. Mol. Cell Biol. 2016, 8(2), 120–128. [Google Scholar] [CrossRef] [PubMed]
- Puchalska, P.; Crawford, P.A. Multi-dimensional Roles of Ketone Bodies in Fuel Metabolism, Signaling, and Therapeutics. Cell Metab. 2017, 25(2), 262–284. [Google Scholar] [CrossRef] [PubMed]
- Youm, Y.; Nguyen, K.Y.; Grant, R.W.; Goldberg, E.L.; Bodogai, M.; Kim, D.; et al. The ketone metabolite beta-hydroxybutyrate blocks NLRP3 inflammasome-mediated inflammatory disease. Nat. Med. 2015, 21(3), 263–269. [Google Scholar] [CrossRef] [PubMed]
- Newman, J.C.; Verdin, E. beta-Hydroxybutyrate: A Signaling Metabolite. Annu Rev. Nutr. 2017, 37, 51–76. [Google Scholar] [CrossRef] [PubMed]
- Evans, M.; Cogan, K.E.; Egan, B. Metabolism of ketone bodies during exercise and training: physiological basis for exogenous supplementation. J. Physiol. 2017, 595(9), 2857–2871. [Google Scholar] [CrossRef] [PubMed]
- Mizushima, N.; Komatsu, M. Autophagy: renovation of cells and tissues. Cell 2011, 147(4), 728–741. [Google Scholar] [CrossRef] [PubMed]
- McLeod, I.X.; Jia, W.; He, Y. The contribution of autophagy to lymphocyte survival and homeostasis. Immunol. Rev. 2012, 249(1), 195–204. [Google Scholar] [CrossRef] [PubMed]
- Rocchi, A.; He, C. Regulation of Exercise-Induced Autophagy in Skeletal Muscle. Curr. Pathobiol. Rep. 2017, 5(2), 177–186. [Google Scholar] [CrossRef] [PubMed]
- Poon, I.K.H.; Lucas, C.D.; Rossi, A.G.; Ravichandran, K.S. Apoptotic cell clearance: basic biology and therapeutic potential. Nat. Rev. Immunol. 2014, 14(3), 166–180. [Google Scholar] [CrossRef] [PubMed]
- Gabay, C.; Kushner, I. Acute-phase proteins and other systemic responses to inflammation. N Engl. J. Med. 1999, 340(6), 448–454. [Google Scholar] [CrossRef] [PubMed]
- Xu, C.; Mutwalli, H.; Haslam, R.; Keeler, J.L.; Treasure, J.; Himmerich, H. C-reactive protein (CRP) levels in people with eating disorders: A systematic review and meta-analysis. J. Psychiatr. Res. 2025, 181, 653–662. [Google Scholar] [CrossRef] [PubMed]
- Swenne, I.; Engstrom, I. Medical assessment of adolescent girls with eating disorders: an evaluation of symptoms and signs of starvation. Acta Paediatr. 2005, 94(10), 1363–1371. [Google Scholar] [CrossRef] [PubMed]
- Evans, S.S.; Repasky, E.A.; Fisher, D.T. Fever and the thermal regulation of immunity: the immune system feels the heat. Nat. Rev. Immunol. 2015, 15(6), 335–349. [Google Scholar] [CrossRef] [PubMed]
- Birmingham, C.L.; Hodgson, D.M.; Fung, J.; Brown, R.; Wakefield, A.; Bartrop, R.; et al. Reduced febrile response to bacterial infection in anorexia nervosa patients. Int. J. Eat. Disord. 2003, 34(2), 269–272. [Google Scholar] [CrossRef] [PubMed]
- Kluger, M.J.; Ringler, D.H.; Anver, M.R. Fever and survival. Science 1975, 188(4184), 166–168. [Google Scholar] [CrossRef]
- Fohlin, L.; Freyschuss, U.; Bjarke, B.; Davies, C.T.; Thoren, C. Function and dimensions of the circulatory system in anorexia nervosa. Acta Paediatr. Scand. 1978, 67(1), 11–16. [Google Scholar] [CrossRef] [PubMed]
- Freyschuss, U.; Fohlin, L.; Thoren, C. Limb circulation in anorexia nervosa. Acta Paediatr. Scand. 1978, 67(2), 225–228. [Google Scholar] [CrossRef] [PubMed]
- Wenisch, C.; Narzt, E.; Sessler, D.I.; Parschalk, B.; Lenhardt, R.; Kurz, A.; et al. Mild intraoperative hypothermia reduces production of reactive oxygen intermediates by polymorphonuclear leukocytes. Anesth. Analg. 1996, 82(4), 810–816. [Google Scholar] [CrossRef]
- Romanovsky, A.A.; Szekely, M. Fever and hypothermia: two adaptive thermoregulatory responses to systemic inflammation. Med. Hypotheses 1998, 50(3), 219–226. [Google Scholar] [CrossRef] [PubMed]
- Liu, E.; Lewis, K.; Al-Saffar, H.; Krall, C.M.; Singh, A.; Kulchitsky, V.A.; et al. Naturally occurring hypothermia is more advantageous than fever in severe forms of lipopolysaccharide- and Escherichia coli-induced systemic inflammation. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2012, 302(12), 1372. [Google Scholar] [CrossRef] [PubMed]
- Wojtaszewski, J.F.P.; Richter, E.A. Effects of acute exercise and training on insulin action and sensitivity: focus on molecular mechanisms in muscle. Essays Biochem 2006, 42, 31–46. [Google Scholar] [CrossRef] [PubMed]
- Dantzer, R.; Kelley, K.W. Twenty years of research on cytokine-induced sickness behavior. Brain Behav. Immun. 2007, 21(2), 153–160. [Google Scholar] [CrossRef] [PubMed]
- Keys; Brozek, A.; Henschel, J.; Mickelsen, A.; O. Taylor, H.L. The Biology of Human Starvation; London Geoffrey Cumberlege Oxford university Press: The University of Minnesota Press: Minneapolis, 1950; Volume 1. [Google Scholar]
- Brown, R.F.; Bartrop, R.; Beumont, P.; Birmingham, C.L. Bacterial infections in anorexia nervosa: delayed recognition increases complications. Int. J. Eat. Disord. 2005, 37(3), 261–265. [Google Scholar] [CrossRef] [PubMed]
- Medzhitov, R.; Schneider, D.S.; Soares, M.P. Disease tolerance as a defense strategy. Science 2012, 335(6071), 936–941. [Google Scholar] [CrossRef] [PubMed]
- Soares, M.P.; Teixeira, L.; Moita, L.F. Disease tolerance and immunity in host protection against infection. Nat. Rev. Immunol. 2017, 17(2), 83–96. [Google Scholar] [CrossRef] [PubMed]
- Durai, V.; Murphy, K.M. Functions of Murine Dendritic Cells. Immunity 2016, 45(4), 719–736. [Google Scholar] [CrossRef] [PubMed]
- Rosales, C. Neutrophil: A Cell with Many Roles in Inflammation or Several Cell Types? Front Physiol. 9, 113. [CrossRef] [PubMed]
- Hutter, G.; Ganepola, S.; Hofmann, W. The hematology of anorexia nervosa. Int. J. Eat. Disord. 2009, 42(4), 293–300. [Google Scholar] [CrossRef] [PubMed]
- Gotch, F.M.; Spry, C.J.; Mowat, A.G.; Beeson, P.B.; Maclennan, I.C. Reversible granulocyte killing defect in anorexia nervosa. Clin. Exp. Immunol. 1975, 21(2), 244–249. [Google Scholar] [PubMed]
- Sadiku, P.; Willson, J.A.; Ryan, E.M.; Sammut, D.; Coelho, P.; Watts, E.R.; et al. Neutrophils Fuel Effective Immune Responses through Gluconeogenesis and Glycogenesis. Cell Metab. 2021, 33(2), 411–423.e4. [Google Scholar] [CrossRef] [PubMed]
- Suzuki, K.; Totsuka, M.; Nakaji, S.; Yamada, M.; Kudoh, S.; Liu, Q.; et al. Endurance exercise causes interaction among stress hormones, cytokines, neutrophil dynamics, and muscle damage. J. Appl. Physiol. (1985) 1999, 87(4), 1360–1367. [Google Scholar] [CrossRef] [PubMed]
- Sadiku, P.; Willson, J.A.; Ryan, E.M.; Sammut, D.; Coelho, P.; Watts, E.R.; et al. Neutrophils Fuel Effective Immune Responses through Gluconeogenesis and Glycogenesis. Cell Metab. 2021, 33(2), 411–423.e4. [Google Scholar] [CrossRef] [PubMed]
- Dantzer, R. Cytokine, sickness behavior, and depression. Immunol. Allergy Clin. North Am. 2009, 29(2), 247–264. [Google Scholar] [CrossRef] [PubMed]
- Murray, P.J.; Wynn, T.A. Protective and pathogenic functions of macrophage subsets. Nat. Rev. Immunol. 2011, 11(11), 723–737. [Google Scholar] [CrossRef] [PubMed]
- Kawanishi, N.; Yano, H.; Yokogawa, Y.; Suzuki, K. Exercise training inhibits inflammation in adipose tissue via both suppression of macrophage infiltration and acceleration of phenotypic switching from M1 to M2 macrophages in high-fat-diet-induced obese mice. Exerc Immunol. Rev. 2010, 16, 105–118. [Google Scholar] [PubMed]
- Murray, P.J.; Allen, J.E.; Biswas, S.K.; Fisher, E.A.; Gilroy, D.W.; Goerdt, S.; et al. Macrophage activation and polarization: nomenclature and experimental guidelines. Immunity 2014, 41(1), 14–20. [Google Scholar] [CrossRef] [PubMed]
- Banchereau, J.; Steinman, R.M. Dendritic cells and the control of immunity. Nature 1998, 392(6673), 245–252. [Google Scholar] [CrossRef] [PubMed]
- Wculek, S.K.; Khouili, S.C.; Priego, E.; Heras-Murillo, I.; Sancho, D. Metabolic Control of Dendritic Cell Functions: Digesting Information. Front Immunol. 2019, 10, 775. [Google Scholar] [CrossRef] [PubMed]
- Collin, M.; McGovern, N.; Haniffa, M. Human dendritic cell subsets. Immunology 2013, 140(1), 22–30. [Google Scholar] [CrossRef] [PubMed]
- O’Neill, L.A.J.; Kishton, R.J.; Rathmell, J. A guide to immunometabolism for immunologists. Nat. Rev. Immunol. 2016, 16(9), 553–565. [Google Scholar] [CrossRef] [PubMed]
- Jain, A.; Pasare, C. Innate Control of Adaptive Immunity: Beyond the Three-Signal Paradigm. J. Immunol. 2017, 198(10), 3791–3800. [Google Scholar] [CrossRef] [PubMed]
- Smith-Garvin, J.E.; Koretzky, G.A.; Jordan, M.S. T cell activation. Annu Rev. Immunol. 2009, 27, 591–619. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Metabolic regulation of immune-cell activation during severe energy restriction. Low circulating leptin reduces leptin receptor signaling, thereby limiting mTORC1 activation, while reduced cellular ATP availability activates AMP-activated protein kinase (AMPK), which further suppresses mTORC1 activity. Together, these signals favor an energy-conserving cellular state rather than the anabolic metabolic reprogramming required for full immune-cell activation and proliferation. Immune cells can generate ATP through glycolysis, which provides rapid but inefficient ATP production, or through mitochondrial oxidative phosphorylation (OXPHOS), which yields substantially more ATP but requires adequate oxygen and metabolic substrates. In acute anorexia nervosa, severe nutrient restriction, potentially compounded by persistent hyperactivity, may therefore shift the AMPK–mTORC1 balance toward energy conservation and constrain energetically demanding immune activation. Abbreviations: AMPK, AMP-activated protein kinase; ATP, adenosine triphosphate; mTORC1, mechanistic target of rapamycin complex 1; OXPHOS, oxidative phosphorylation.
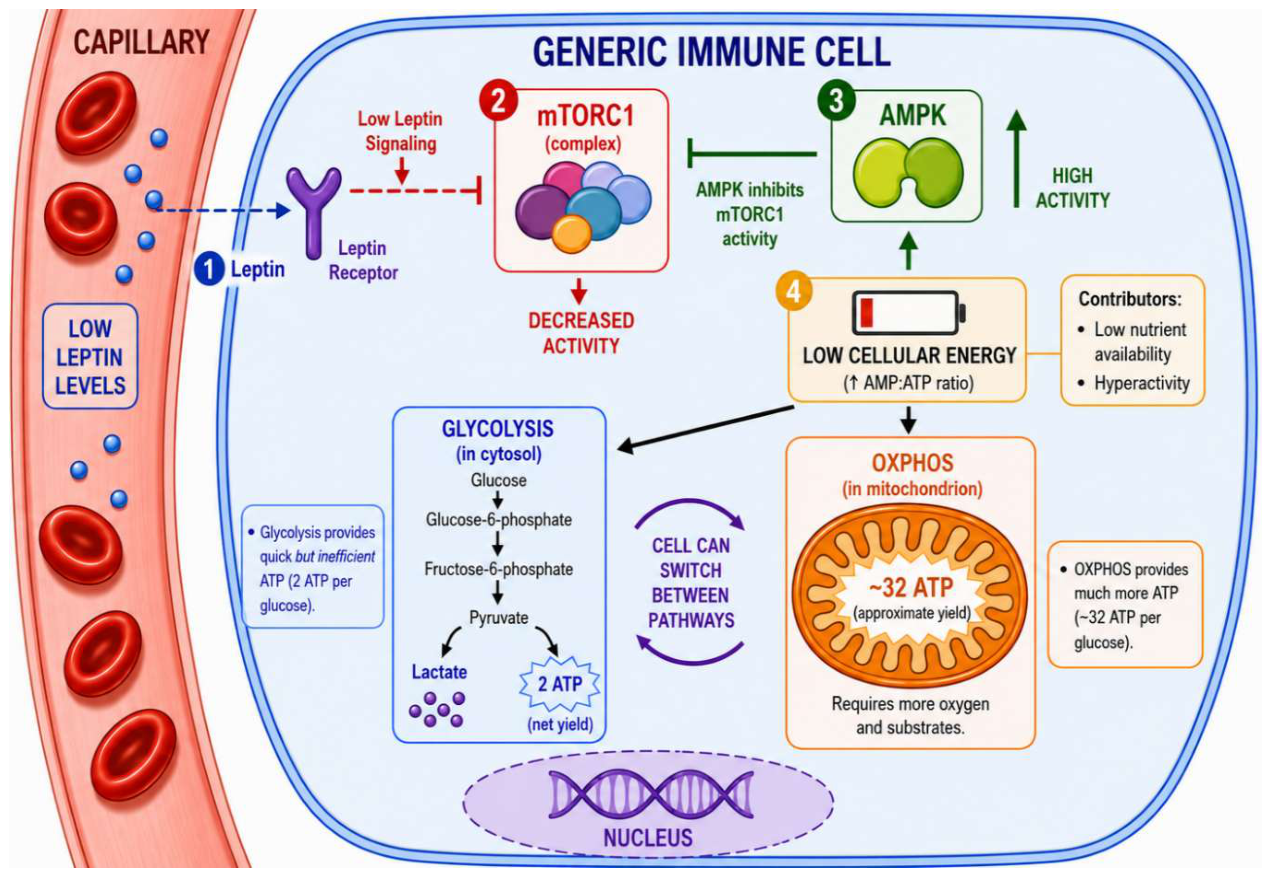
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.