

Submitted:
14 August 2026
Posted:
14 August 2026
You are already at the latest version
Abstract
Halo-gravity traction (HGT) is widely used as a preoperative treatment for severe pediatric spinal deformities by gradually applying traction forces through a cranial fixation system. While the clinical effectiveness of HGT has been extensively documented, the uncertainty associated with the structural performance and operational reliability of mobile HGT systems has received comparatively little attention. This study presents a coupled clinical–structural uncertainty quantification framework for the evaluation of a mobile halo-gravity traction wheelchair. Reduced-order structural and clinical response models are combined with Monte Carlo simulation, Latin Hypercube Sampling, bounded beta-distributed input variables, Polynomial Chaos Expansion, and Sobol sensitivity analysis to propagate uncertainty from patient, operational, and design parameters to structural response metrics. The framework evaluates structural integrity, stability, halo-pin loading, traction delivery, factors of safety, and representative clinical response measures. The probabilistic analysis demonstrates that the proposed design maintains substantial structural safety margins throughout the investigated uncertainty space, with no sampled realization producing a governing factor of safety below unity. The proposed framework provides an efficient methodology for uncertainty-informed design and evaluation of pediatric halo-gravity traction systems.
Keywords:
halo-gravity traction
; uncertainty quantification
; polynomial chaos expansion
; Monte Carlo simulation
; structural reliability
; medical device design
1. Introduction
1.1. Uncertainty Quantification in Biomedical Engineering
Finite element analysis (FEA) has become an established tool in computational biomechanics for the design and evaluation of orthopedic implants and medical devices, including hip and knee replacements, spinal fixation systems, fracture fixation devices, and dental implants. Numerous studies have employed FEA to evaluate implant stresses, optimize device geometry, improve fatigue performance, and develop patient-specific treatment strategies. More recently, uncertainty quantification (UQ) has become increasingly important in computational biomechanics and medical device evaluation by accounting for variability in material properties, anatomical geometry, implant positioning, physiological loading, and other model parameters. These probabilistic approaches improve confidence in computational predictions and provide a more rigorous assessment of device performance than traditional deterministic analyses [1,2,3,4].
Recent research has consequently shifted from deterministic finite element analyses toward probabilistic computational frameworks capable of propagating uncertainties through biomechanical models. Monte Carlo simulation, Polynomial Chaos Expansion (PCE), and verification, validation, and uncertainty quantification (VVUQ) methodologies have been successfully applied to orthopedic biomechanics, patient-specific analyses, spinal fixation systems, cardiovascular devices, and other implantable medical systems. These approaches enable engineers to quantify the influence of uncertain design variables on stresses, strains, fatigue life, and structural reliability while providing a more realistic assessment of device performance than deterministic methods alone.
Among the available uncertainty propagation techniques, Polynomial Chaos Expansion (PCE) has emerged as one of the most effective surrogate modeling approaches because it represents stochastic system responses using orthogonal polynomial basis functions defined over the probability space of uncertain input variables. Since the generalized polynomial chaos framework introduced by Xiu and Karniadakis [5,6], considerable research has focused on improving the efficiency, scalability, and robustness of PCE for practical engineering applications. These developments include adaptive and weighted least-squares formulations, basis adaptivity, sequential adaptive sampling, and classifier-based sparse expansions for high-dimensional stochastic systems [7,8,9], sensitivity-enhanced polynomial chaos methods for improved uncertainty propagation in nonlinear and chaotic systems [10,11], and efficient algorithms for dynamic systems, reliability analysis, and uncertainty-informed design optimization [12,13,14,15]. Collectively, these advances have substantially reduced the computational cost associated with uncertainty propagation while maintaining predictive accuracy comparable to conventional Monte Carlo simulation, making PCE an attractive methodology for engineering design, reliability assessment, sensitivity analysis, and uncertainty-informed decision making.
Despite these advances, uncertainty-aware computational methods have been applied primarily to implantable orthopedic devices, cardiovascular systems, and patient-specific biomechanical analyses. Comparatively little attention has been devoted to orthopedic treatment systems whose primary purpose is the application of controlled therapeutic loads rather than permanent implantation. Halo-gravity traction represents one such application, where patient variability, loading uncertainty, and structural response interact to determine both treatment effectiveness and device safety.
1.2. Halo-Gravity Traction Systems
Halo-gravity traction (HGT) is a gradual correction technique used for patients with severe spinal deformities, particularly pediatric scoliosis and kyphoscoliosis. Controlled traction is applied through a halo ring secured to the skull, allowing the spine, surrounding soft tissues, ligaments, and musculoskeletal structures to deform progressively over a period of days or weeks before definitive corrective surgery. Beyond reducing spinal deformity, HGT improves surgical preparation, reduces the magnitude of acute intraoperative correction, and often improves respiratory function and nutritional status in medically fragile patients.
Clinical studies have demonstrated that HGT typically produces deformity corrections on the order of 25–40%, together with measurable improvements in pulmonary capacity and overall preoperative condition [16,17,18,19,20]. However, treatment outcomes exhibit substantial patient-to-patient variability because correction depends on factors including initial deformity severity, patient anatomy, spinal flexibility, traction-force progression, treatment duration, and pin placement. Furthermore, the spine and surrounding tissues exhibit time-dependent viscoelastic behavior, so correction develops gradually through tissue creep, ligament deformation, muscle relaxation, and structural adaptation under sustained loading rather than as an instantaneous elastic response [17,21].
The mechanical system used to deliver halo-gravity traction also contributes significantly to treatment performance. Conventional HGT systems commonly employ suspended weights, pulley mechanisms, hospital beds, wheelchairs, and manually assembled support structures. While clinically effective, these systems introduce engineering uncertainties associated with pulley friction, structural flexibility, caregiver handling, patient motion, wheelchair acceleration, and load transfer through the halo ring [22,23,24]. As a result, the actual traction load delivered to the patient may differ from the prescribed load, while structural components experience uncertain loading conditions that influence safety and long-term durability.
The mobile halo-gravity traction wheelchair considered in the present study was originally conceived, designed, and prototyped through a senior biomedical engineering capstone project conducted at the University of Alabama at Birmingham. Rather than revisiting the device-design process itself, the present work builds upon the completed prototype to perform a comprehensive uncertainty-informed engineering evaluation. The system integrates a wheelchair, vertical support member, guided weight carriage, pulley-and-cable traction mechanism, welded rear support frame, anti-tip caster supports, and attachment hardware into a single structural system intended to improve traction delivery during patient mobility.
Because the device operates at the intersection of clinical treatment and structural mechanics, it must simultaneously satisfy requirements related to traction delivery, structural stresses, buckling resistance, weld integrity, tipping stability, and halo-pin loading. Each of these responses depends on uncertain patient characteristics, operational conditions, and structural parameters, making deterministic evaluation insufficient for establishing overall system performance. Consequently, the present study develops a coupled clinical–structural uncertainty quantification framework that combines Monte Carlo simulation, Latin Hypercube Sampling (LHS), bounded beta-distributed input variables, Polynomial Chaos Expansion, and Sobol sensitivity analysis to identify the dominant sources of uncertainty and the governing structural safety margins.
The primary contribution of this work is the integration of clinical loading concepts with structural uncertainty analysis for a mobile HGT wheelchair system. Rather than treating the wheelchair attachment, support frame, pulley system, and halo-pin load transfer as independent problems, the proposed reduced-order framework evaluates them simultaneously in terms of structural integrity, traction delivery, buckling resistance, weld performance, halo-pin loading, and overall system reliability. The resulting probabilistic model provides a practical engineering tool for identifying the parameters that govern system performance and for guiding future structural redesign, experimental validation, and clinical implementation.
2. System Description and Structural Modeling
The halo-gravity traction (HGT) wheelchair system is designed as a mobile pediatric traction platform for continuous clinical use during the preoperative treatment of severe scoliosis and kyphosis. The system combines a conventional wheelchair base with an integrated rear structural support assembly that carries the guided traction-weight system and the associated cable-and-pulley hardware. The primary load-carrying member is a vertical C-channel support welded to the rear frame of the wheelchair. A guided carriage travels along this member and supports the traction weights, while the pulley system redirects the applied load to the halo ring. Rear caster supports extend the effective support polygon of the wheelchair and improve resistance to rearward tipping during operation.
Figure 1 presents both the fabricated prototype and the corresponding CAD model that form the basis of the reduced-order uncertainty quantification framework developed in this study. The integrated rear support frame, guided vertical boom, overhead traction assembly, and rear caster supports are visible in both configurations. The prototype was developed to provide continuous traction during patient transport while maintaining the mobility and dimensional requirements of a conventional hospital wheelchair.
Because the system is intended for routine hospital use, its overall dimensions must remain compatible with standard patient rooms, hallways, elevators, and door openings. Accordingly, the principal geometric constraints are
and
where and denote the overall system width and height, respectively. These dimensional limitations influence considerably more than the external package size. They directly affect the available base width, the placement of the rear caster supports, the height of the vertical boom, the pulley location, and the overall traction-line geometry. Consequently, dimensional design choices influence both clinical usability and structural stability.
During treatment, the prescribed traction force is increased gradually until the desired therapeutic loading level is achieved. A representative upper bound may be expressed as
where denotes the patient body weight. Although the exact traction ratio is determined clinically according to patient tolerance, treatment stage, and deformity severity, this relationship illustrates the strong coupling between patient weight and structural loading. Larger patient weights generally require higher traction loads, thereby increasing the compressive loading within the support structure, halo-pin forces, pulley reactions, and weld loads throughout the wheelchair assembly.
The structural load path originates at the halo ring, where the prescribed traction force is applied to the patient. The resulting cable tension is transmitted through the pulley system to the guided weight carriage, then into the vertical support member, the welded rear frame, the rear caster supports, the wheelchair attachment points, and finally the ground. Experimental observations obtained during prototype evaluation indicate that the rear support frame and caster assembly carry a substantial portion of the global structural reaction.
For the member-level structural analysis presented in this work, the vertical support is conservatively idealized as a fixed-free cantilever beam-column. The traction load is transferred through the short horizontal arm at a finite eccentricity from the centroidal axis of the vertical support. Consequently, the member experiences simultaneous axial compression, first-order eccentric bending, and second-order geometric amplification (P-) rather than pure column compression. This beam-column representation more accurately reflects the actual load path of the prototype than a conventional concentrically loaded Euler column.
The principal structural response mechanisms considered in the reduced-order model include axial cable loading, compressive loading of the vertical support member, local contact forces between the guided carriage and the support, welded-joint loading, dynamic inertial loading associated with wheelchair motion. Because the carriage is mechanically guided, large pendulum-type oscillations commonly associated with suspended-weight systems are substantially reduced. Nevertheless, patient motion, wheelchair acceleration, floor transitions, sudden starts and stops, and minor geometric misalignment may still introduce additional dynamic loading and secondary bending effects that contribute to the overall uncertainty in the structural response.
The vertical support member is fixed to the wheelchair frame and carries the traction load through the short horizontal arm. It is therefore modeled as an eccentrically loaded cantilever beam–column. A first-order estimate of the equivalent compressive load is
where is the prescribed traction force and is the additional dynamic load associated with wheelchair acceleration or stopping.
The average axial compressive stress is
where is the effective cross-sectional area of the vertical support. For the fixed–free idealization, the effective-length factor is fixed at , and the Euler critical load is
where E is Young’s modulus, is the smaller principal second moment of area, and is the unsupported vertical length.
The first-order moment caused by the horizontal offset of the suspended load is
where is the horizontal distance from the centroidal axis of the vertical member to the load line at the end of the short horizontal arm. A reduced-order second-order magnification is used to account for the P– effect,
for . The corresponding extreme-fiber compressive stress is
where c is the distance from the neutral axis to the extreme fiber. The Euler buckling and combined beam–column factors of safety are defined as
and
respectively, where is the material yield strength and is the fabrication-efficiency factor. The combined factor of safety accounts for direct compression, eccentric bending, and elastic moment magnification, whereas retains the global Euler instability check.
Dynamic inertial loading associated with wheelchair motion is approximated as
where is the moving weight mass and a is wheelchair acceleration. This term is included because the system is intended to be mobile. Even if the static traction load is controlled carefully, movement through a hospital environment can introduce additional loads through starts, stops, turns, uneven flooring, and patient motion. In the present reduced-order framework, these effects are not modeled with a full multibody dynamic simulation; instead, they are represented through uncertain operational acceleration and load-amplification parameters so that their influence on structural safety can be screened.
3. Tipping Stability Considerations
Tipping stability was examined during the development of the reduced-order structural model to determine whether it should be included as an additional limit state in the uncertainty analysis. Rearward tipping would occur about the ground-contact line associated with the rear caster supports, and the direction of the moment produced by each vertical load depends on its horizontal position relative to this tipping axis rather than on its height above the ground.
In the present configuration, the traction-load line is located forward of the vertical support member and forward of the rear caster support axis. Consequently, the traction-related vertical load produces a restoring moment rather than an overturning moment. Likewise, the patient weight, the wheelchair/support-system weight, and the guided weight-stack load all act forward of the rear support boundary and therefore contribute to overall stability.
The rear caster supports substantially extend the wheelchair support polygon, thereby increasing the available restoring moment against rearward rotation. Under the quasi-static loading conditions considered in this study, all primary vertical loads remain within the support polygon, and no realistic loading scenario associated with normal operation produces a tendency for the system to tip.
Because tipping is not a credible failure mode for the fixed-base HALO traction chair considered here, it was excluded from the structural limit states used in the uncertainty quantification framework. Potential instability resulting from abnormal impact, abrupt wheelchair acceleration, or misuse lies outside the scope of the present investigation.
4. Welded Joint and Fatigue Analysis
The welded joints connecting the vertical support member, rear structural frame, caster supports, and wheelchair attachment members represent critical structural regions because they transfer the majority of the applied loads between the primary structural components. During clinical operation these joints are subjected not only to static loading arising from the prescribed traction force, but also to cyclic loading generated by wheelchair motion, patient movement, and repeated loading and unloading during routine use. Consequently, weld integrity and fatigue resistance are included explicitly among the structural limit states considered in the present uncertainty quantification framework.
For the reduced-order structural model, the average weld-throat shear stress is approximated by
where F is the resultant force transmitted through the welded joint and is the effective weld-throat area.
The corresponding weld factor of safety is defined as
where is the allowable weld shear stress determined from the selected material, weld geometry, and applicable design criteria. This factor of safety provides a first-order assessment of the available static weld capacity throughout the uncertainty space.
Although the wheelchair operates primarily under quasi-static loading, repeated patient transport and routine clinical use introduce cyclic stress variations within the welded connections. These stress fluctuations are approximated by
where and denote the maximum and minimum stresses experienced during a representative loading cycle. The corresponding fatigue life may then be estimated using
where represents the appropriate material fatigue relationship.
The present reduced-order uncertainty framework is intended primarily to identify the dominant sources of structural variability rather than to perform a detailed fatigue-life prediction. Accordingly, weld quality, fabrication variability, and fatigue-related parameters are incorporated as uncertain quantities whose influence on the overall structural response can be evaluated together with the remaining limit states. This approach provides a practical means of assessing the relative importance of weld performance while avoiding the computational expense of a detailed local finite-element fatigue analysis.
5. Coupled Clinical–Structural Uncertainty Model
The proposed halo-gravity traction (HGT) wheelchair should be viewed as a coupled clinical–structural system rather than simply as a static mechanical structure. Although the primary engineering objectives include maintaining adequate structural integrity, buckling resistance, weld safety, and acceptable halo-pin loading, the ultimate purpose of the device is the safe and reliable delivery of prescribed spinal traction throughout an extended treatment period. Consequently, uncertainty originates not only from the mechanical system itself but also from patient characteristics, clinical operating conditions, and manufacturing variability.
The uncertainty quantification framework therefore combines three interacting sources of uncertainty:
- 1.
- patient-specific clinical uncertainty,
- 2.
- device design and manufacturing uncertainty, and
- 3.
- structural response and safety-margin uncertainty.
Unlike conventional structural reliability analyses that consider only material or geometric variability, the present framework propagates uncertainty originating from both the clinical treatment process and the structural support system. This coupled approach provides a more realistic assessment of the operational reliability of the HGT wheelchair under representative clinical conditions.
5.1. Clinical Input Variables
The patient-level uncertainty vector is defined as
where denotes the patient body weight, is the prescribed traction-load ratio, is the treatment duration, is an effective spinal-stiffness surrogate parameter, and represents the severity of the spinal deformity.
The prescribed traction force is modeled as
subject to
Because the prescribed traction force is determined directly from the patient body weight, and are treated as physically coupled quantities rather than statistically independent random variables. This relationship preserves the clinical dependency between patient size and the therapeutic traction force.
5.2. Clinical Response Approximation
To provide a representative clinical response metric, the spinal elongation is approximated using the reduced-order relationship
where is an effective spinal-stiffness surrogate parameter representing the average global stiffness of the patient spine. Because validated patient-specific clinical datasets are not currently available, this quantity should be interpreted as a reduced-order surrogate response intended to illustrate the propagation of clinical uncertainty rather than to predict patient-specific clinical outcomes.
5.3. Device and Manufacturing Variables
The device-level uncertainty vector is defined as
These quantities describe the principal sources of uncertainty associated with the structural design, fabrication, halo-pin load transfer, and operational loading of the HGT wheelchair. Specifically, denotes the number of active halo pins, is the allowable load carried by each halo pin, represents the pin-load eccentricity amplification factor, and characterizes the efficiency of load sharing among the halo pins. The variables and represent the effective cross-sectional area and weak-axis second moment of area of the vertical support member, respectively, while denotes the eccentricity between the applied traction load and the centroidal axis of the vertical support. The fabrication efficiency is represented by . Finally, represents the operational wheelchair acceleration normalized by gravitational acceleration and accounts for additional structural loading associated with starting, stopping, and maneuvering.
The elastic modulus, unsupported column length, and fixed–free support condition are treated as deterministic quantities in the present screening study, with nominal values of , , and , respectively. These quantities are held fixed because their expected variability is substantially smaller than the variability associated with patient loading, geometric tolerances, fabrication quality, and clinical operation.
The delivered traction force may differ from the suspended weight because of frictional losses within the pulley system. If denotes the gravitational force produced by the suspended weight stack, the delivered traction force is approximated by
where represents the overall mechanical efficiency of the pulley system. This relationship allows uncertainty associated with pulley friction and mechanical losses to be propagated together with the remaining clinical and structural uncertainty sources.
5.4. Halo-Pin Load and Stability Model
The halo-pin subsystem represents one of the most mechanically critical components of the halo-gravity traction system because the prescribed traction force is ultimately transmitted to the patient through a limited number of cranial fixation pins. Consequently, both the magnitude of the applied traction load and the distribution of that load among the individual pins directly influence patient safety and overall system reliability.
Assuming that the prescribed traction force is shared equally among active halo pins, the average load carried by each pin is approximated by
In practice, however, manufacturing tolerances, slight geometric misalignment, variations in pin insertion, and local anatomical differences generally produce nonuniform load sharing. To account for these effects, the maximum load carried by an individual pin is represented by the simplified relationship
where is an eccentricity amplification factor that accounts for nonuniform loading and is the corresponding pin load-sharing efficiency factor. Together these parameters provide a reduced-order representation of the mechanical variability associated with the halo fixation system.
The corresponding halo-pin factor of safety is defined as
where denotes the allowable load for an individual halo pin based on accepted clinical practice and the corresponding mechanical design limits.
5.5. Combined System Response
The reduced-order uncertainty framework combines the clinical and structural models into a single coupled input–output relationship,
where and denote the clinical and device-level uncertainty vectors, respectively. This mapping propagates uncertainty originating from patient characteristics, treatment parameters, manufacturing variability, and structural properties to the quantities governing both structural safety and representative clinical performance.
The corresponding response vector is defined as
which includes the principal structural stresses, stability measures, factors of safety, representative clinical response, and the overall probability of structural failure.
Failure within the reduced-order framework is characterized using the indicator function
where denotes the governing limit-state function associated with the complete coupled clinical–structural model. The corresponding probability of failure is therefore expressed as
which represents the probability that any governing structural limit state is violated within the prescribed uncertainty space.
5.6. Modeling Scope
The proposed formulation should be interpreted as a reduced-order engineering uncertainty framework intended to evaluate the structural reliability and operational robustness of the halo-gravity traction wheelchair rather than to predict patient-specific clinical outcomes. The structural models were developed to provide computationally efficient surrogate representations of the governing load paths, stability mechanisms, and safety margins while preserving the dominant physics required for uncertainty propagation and global sensitivity analysis. Consequently, the framework is intended to support preliminary engineering design, uncertainty screening, and reliability assessment prior to detailed finite-element modeling and experimental validation.
5.7. Design Implications
The principal contribution of the present work is the development of a unified coupled clinical–structural uncertainty quantification framework for evaluating halo-gravity traction systems. By simultaneously propagating uncertainty arising from patient characteristics, prescribed traction loading, device geometry, fabrication variability, and operational conditions, the framework identifies the dominant factors governing structural reliability and clinical performance.
The resulting sensitivity information provides direct guidance for future design refinement by identifying the parameters that most strongly influence beam–column behavior, weld integrity, halo-pin loading, traction-force delivery, and overall structural reliability. Rather than relying solely on deterministic safety factors, the proposed methodology provides a quantitative basis for prioritizing structural modifications, reducing performance variability, and supporting future finite-element analyses, experimental validation, and optimization of pediatric halo-gravity traction systems.
6. Uncertainty Quantification Methodology
The halo-gravity traction wheelchair system contains uncertainty associated with patient characteristics, prescribed traction loading, wheelchair motion, structural geometry, fabrication quality, halo-pin load sharing, and operational conditions. Consequently, deterministic calculations alone are insufficient for assessing structural safety over the full range of anticipated clinical operation.
The present work therefore employs uncertainty quantification (UQ) to propagate uncertainty in the model inputs through the reduced-order structural model and to quantify the resulting variability in the principal structural safety measures and representative clinical-response quantities.
The complete uncertain input vector is defined as
The uncertain variables, their physical interpretation, and the bounded ranges adopted in the present study are summarized in Table 1. Unless otherwise stated, each uncertain input is represented using a bounded beta distribution defined over the corresponding interval..
The uncertainty bounds listed in Table 1 are intended to represent physically reasonable engineering estimates rather than statistically measured population distributions. The selected ranges encompass expected variability associated with patient characteristics, clinical operation, fabrication tolerances, geometric uncertainty, and simplified reduced-order modeling assumptions. Bounded beta distributions were selected because they provide flexible probability-density functions while ensuring that all sampled realizations remain within physically meaningful limits.
The prescribed traction force is computed from
where is the prescribed traction-load ratio and is the patient body weight. Because the prescribed traction force is determined directly from the patient weight, these quantities are treated as physically coupled throughout the uncertainty analysis rather than as statistically independent variables.
Within the present reduced-order framework, the delivered traction force propagated through the uncertainty analysis is assumed to equal the prescribed traction force,
Mechanical losses associated with the pulley system and guided carriage are not introduced as a reduction in the reported delivered traction. Instead, these effects are incorporated within the internal structural load path used to estimate the suspended-weight loading and the corresponding inertial forces acting on the support structure.
Dynamic inertial loading associated with wheelchair motion is represented by
where is the suspended moving weight and a is the wheelchair acceleration. This simplified expression provides a first-order approximation of the additional structural loading generated during starts, stops, turning maneuvers, and routine patient transport.
The corresponding uncertain response vector is defined as
which contains the principal structural safety measures, representative clinical surrogate quantities, and the binary structural failure indicator used throughout the uncertainty propagation.
To provide a single measure of the overall structural performance, the governing factor of safety is defined as
so that the governing structural limit state is identified automatically for every uncertainty realization. This formulation permits the competing structural mechanisms—including global Euler buckling, eccentric beam–column response, weld integrity, and halo-pin loading—to be evaluated simultaneously within a unified uncertainty quantification framework. The resulting response distributions are subsequently used to estimate response statistics, identify the governing structural mode, and quantify the relative importance of each uncertain input through global sensitivity analysis.
6.1. Latin Hypercube Sampling and Beta Distributions
The uncertain input variables are sampled using Latin Hypercube Sampling (LHS) in conjunction with bounded beta probability distributions. LHS provides a stratified sampling strategy that improves coverage of the multidimensional uncertainty space while requiring substantially fewer realizations than conventional random Monte Carlo sampling. This improved sampling efficiency is particularly advantageous for the present high-dimensional uncertainty propagation study.
Each uncertain variable is represented by a beta distribution defined over a finite interval. Unlike Gaussian distributions, beta distributions possess bounded support and therefore prevent the generation of physically unrealistic parameter values outside the prescribed engineering limits. In addition, the beta distribution provides sufficient flexibility to represent symmetric, positively skewed, negatively skewed, or nearly uniform uncertainty through appropriate selection of its shape parameters.
For an uncertain variable bounded by and , a normalized beta-distributed sample is mapped to the corresponding physical interval according to
The corresponding beta probability density function is
where and denote the beta-distribution shape parameters and is the beta function.
Several combinations of are investigated to examine the influence of distribution shape on the propagated response statistics, probability-of-failure estimates, and global sensitivity rankings. This approach enables the proposed framework to assess not only the effects of uncertainty magnitude but also the influence of different probabilistic assumptions regarding the underlying input variables.
6.2. Polynomial Chaos Expansion
Polynomial Chaos Expansion (PCE) is employed to construct computationally efficient surrogate models of the reduced-order clinical–structural response. Once the surrogate model has been established, statistical moments, probability distributions, and global sensitivity indices may be evaluated with substantially lower computational cost than repeated direct evaluations of the underlying model.
The uncertain system response is approximated by
where are the expansion coefficients and are orthogonal multivariate polynomial basis functions defined over the uncertain parameter space.
Because all uncertain input variables are represented using bounded beta probability distributions, Jacobi polynomial basis functions are employed throughout the present framework. This choice preserves orthogonality with respect to the assumed input distributions and provides an efficient spectral representation of the reduced-order response surface.
6.3. Sobol Sensitivity Analysis
Global sensitivity analysis is performed using Sobol sensitivity indices computed from the Polynomial Chaos Expansion. The resulting indices quantify the relative contribution of each uncertain input variable to the overall response variance and thereby identify the dominant sources of uncertainty governing the structural behavior of the HGT wheelchair.
The first-order Sobol sensitivity index associated with variable is defined as
The corresponding total Sobol index is
where denotes the complete set of uncertain variables excluding .
The resulting sensitivity indices provide a quantitative ranking of the uncertain input variables according to their contribution to the propagated response variance. This information identifies the dominant parameters governing structural reliability and provides direct guidance for future structural redesign, manufacturing improvements, uncertainty reduction, and operational refinement.
Because the present uncertainty framework is based on reduced-order structural and clinical surrogate models, the resulting sensitivity indices should be interpreted primarily as engineering uncertainty-screening measures rather than patient-specific clinical predictions. Additional uncertainty associated with spinal biomechanics, patient motion, caregiver operation, and long-term halo-pin biomechanics remains only approximately characterized because of the limited availability of validated experimental and clinical datasets.
Finally, each uncertainty realization is classified according to its governing structural limit state. Depending on the propagated uncertainty realization, the controlling response may correspond to combined beam–column loading, global elastic buckling, weld failure, halo-pin overload, or other competing structural mechanisms. This classification provides additional insight into the relative importance of the individual failure mechanisms beyond the corresponding probability-of-failure estimates.
7. Results and Discussion
The proposed uncertainty quantification framework produces a comprehensive set of structural, operational, and clinical surrogate response quantities for the coupled halo-gravity traction (HGT) wheelchair system. These responses include beam–column stability, combined axial–bending behavior, weld integrity, halo-pin loading, delivered traction force, representative clinical response metrics, and overall structural reliability. Together, these responses provide a probabilistic assessment of the mechanical performance of the HGT system under representative clinical operating conditions.
Unlike conventional deterministic structural analyses, the present methodology propagates uncertainty originating from patient characteristics, treatment parameters, structural geometry, fabrication variability, and operational loading simultaneously through the coupled clinical–structural model. The resulting response distributions therefore quantify not only the expected structural behavior, but also the variability and reliability associated with realistic clinical operation.
The propagated results demonstrate that the HGT wheelchair behaves as a coupled patient–device system rather than as an isolated static structure. Patient weight, prescribed traction loading, wheelchair acceleration, support-member geometry, fabrication variability, and halo-pin load sharing interact to influence the resulting structural response. Consequently, no individual parameter alone governs the overall system behavior; instead, the observed response is produced by the combined interaction of clinical loading conditions and structural design variables.
The following sections examine the resulting response distributions, governing structural limit states, global sensitivity rankings, and probability-of-failure estimates obtained from the uncertainty propagation analysis. Particular attention is given to identifying the dominant sources of response variability and the structural mechanisms governing the overall reliability of the proposed HGT wheelchair.
7.1. Probabilistic Structural and Operational Results
The coupled clinical–structural uncertainty model was evaluated using Monte Carlo simulation in conjunction with Latin Hypercube Sampling and bounded beta-distributed input variables. The resulting response distributions provide a probabilistic assessment of the structural performance and operational behavior of the proposed halo-gravity traction (HGT) wheelchair over the prescribed uncertainty space.
The primary structural response quantity considered throughout the present study is the governing minimum factor of safety,
which identifies the controlling structural limit state for each uncertainty realization. This formulation allows competing failure mechanisms—including global elastic buckling, combined beam–column response, weld integrity, and halo-pin loading—to be evaluated simultaneously within a unified reliability framework.
Table 2 summarizes the principal probabilistic response statistics obtained from the uncertainty propagation analysis. For each response quantity, the mean together with the 5th, 50th, and 95th percentiles are reported in order to characterize both the central tendency and the dispersion of the predicted structural behavior.
The probabilistic response statistics indicate that the proposed HGT wheelchair maintains substantial structural safety margins throughout the prescribed uncertainty space. Although all structural limit states remain well above their corresponding failure thresholds, the governing factor of safety varies across the uncertainty realizations because of the combined influence of patient characteristics, prescribed traction loading, structural geometry, fabrication variability, and operational conditions. The subsequent sections examine these response distributions in greater detail and identify the dominant structural mechanisms responsible for the observed uncertainty propagation.
Figure 2 shows the probability-density distribution of the governing minimum factor of safety. The uncertainty propagation produced a mean value of approximately 18.65 with a 5th–95th percentile interval extending from approximately 8.66 to 34.09. No uncertainty realization produced , indicating that all simulated cases remained within the prescribed structural safety limits.
Although the governing factor of safety is substantially lower than the individual Euler buckling and weld safety margins, the revised eccentric beam–column formulation provides a more realistic representation of the structural response by accounting for combined axial compression, eccentric bending, and elastic moment magnification.
The screening Sobol indices shown in Figure 3 indicate that uncertainty in the governing minimum factor of safety is influenced primarily by the halo-pin subsystem together with the prescribed traction loading. The allowable halo-pin load, pin eccentricity amplification, number of active pins, traction ratio, and pin load-sharing efficiency exhibit the largest screening indices. These parameters directly influence the transmitted traction load and therefore affect both halo-pin loading and the combined beam–column response of the vertical support. Material properties and structural-section parameters contribute comparatively smaller sensitivity indices within the investigated uncertainty space.
The propagated halo-pin factor-of-safety distribution shown in Figure 4 produced a mean value of approximately 19.08 with a 5th–95th percentile interval extending from approximately 8.69 to 35.52. No uncertainty realization produced , indicating that the predicted pin loads remained below the allowable limit throughout the investigated uncertainty space.
Figure 5 summarizes the governing structural mode for all uncertainty realizations. The eccentric beam–column formulation predicts that the combined compression–bending response governs approximately 90% of all realizations. Halo-pin loading governs approximately 9% of the simulated cases. These results demonstrate that eccentric beam–column behavior, represents the critical structural mechanism for the present design.
The delivered traction-force distribution shown in Figure 6 produced a mean value of approximately 27.09 lb with a 5th–95th percentile interval extending from approximately 12.02 lb to 45.67 lb. In the present formulation the delivered traction force is taken to be equal to the prescribed traction force. Pulley and carriage losses are retained only within the internal structural load-path calculations and are not treated as reductions in the reported delivered traction response.
The present framework additionally incorporates a reduced-order clinical surrogate intended to represent the coupling between delivered traction and approximate treatment response.
The spinal elongation surrogate is represented by
and the normalized clinical response is defined as
where denotes a representative normalization quantity. The propagated distribution shown in Figure 7 produced a mean value of approximately 0.612 with a 5th–95th percentile interval extending from approximately 0.324 to 0.971.
Overall, the uncertainty-propagation framework demonstrates that the present halo-gravity traction wheelchair maintains comfortable structural safety margins throughout the prescribed uncertainty space. The beam–column model used shows that combined compression and eccentric bending dominate the structural response, whereas classical Euler buckling, weld failure remain comparatively unlikely governing mechanisms.
7.2. Design Interpretation and Future Structural Refinement
The uncertainty-propagation results provide additional insight beyond simple structural safety assessment. The present configuration maintained relatively large structural margins throughout the investigated uncertainty space, with no sampled realization producing . Consequently, the dominant engineering challenge for future development is not necessarily increasing nominal structural strength, but rather reducing sensitivity to operational and geometric uncertainty sources.
Advanced composite materials can provide significantly higher specific stiffness, , and specific strength, , than conventional metallic structures, where E is the elastic modulus, is the ultimate strength, and is the material density. Carbon-fiber-reinforced polymer laminates can therefore substantially reduce structural mass while maintaining or increasing load-carrying capability.
8. Conclusions
A coupled uncertainty-quantification framework for a halo-gravity traction wheelchair system was developed using reduced-order structural, operational, and clinical-surrogate models combined with Monte Carlo simulation, Latin Hypercube Sampling, Polynomial Chaos Expansion, and Sobol global sensitivity analysis.
The proposed framework treats the halo-gravity traction wheelchair as a coupled patient–device system in which uncertainty propagates simultaneously through traction loading, wheelchair operating conditions, structural response, fabrication variability, pulley behavior, and halo-pin mechanics. The uncertainty-propagation analyses showed that the structural response is governed primarily by operational loading behavior, traction-delivery variability, geometric loading conditions, and halo-pin load-sharing characteristics, while global material yielding and structural instability remain comparatively less influential within the investigated uncertainty space.
The uncertainty quantification results further demonstrate that the proposed halo-gravity traction wheelchair maintains satisfactory structural performance throughout the prescribed uncertainty space. The governing factor of safety was evaluated using the principal structural limit states within a unified reliability framework, allowing the controlling failure mechanism to be identified for every uncertainty realization. No sampled realization produced a governing factor of safety below unity, indicating that the proposed design remained structurally stable for all simulated combinations of patient, operational, manufacturing, and geometric uncertainties.
Overall, the present work establishes a probabilistic engineering framework for evaluating coupled structural response under realistic operating conditions in mobile halo-gravity traction systems. The methodology provides an efficient approach for quantifying structural reliability, identifying the dominant sources of uncertainty, and supporting future structural optimization, experimental validation, operational testing, and continued engineering development of halo-gravity traction systems.
Author Contributions
Conceptualization, [A.O. S.M.O.]; methodology, [A.O., S.B.M., S.M.O., J.B., E.P.]; software, [S.B.M. and S.M.O.]; validation, [S.B.M.]; formal analysis, [S.B.M., M.S.O., E.P., J.B.]; investigation, [A.O., S.M.O.]; resources, [A.O. and S.M.O.]; data curation, [A.O.]; writing—original draft preparation, [S.M.O., A.O.]; writing—review and editing, [S.B.M., J.B., E.P., A.O.]; visualization, [—]; supervision, [S.M.O.]; project administration, [—]. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data presented in this study are available from the corresponding author upon reasonable request.
Conflicts of Interest
The authors declare no conflicts of interest.
Acknowledgments
The authors acknowledge the contributions of the University of Alabama at Birmingham senior biomedical engineering capstone team involved in the original development and fabrication of the halo-gravity traction wheelchair prototype.
Nomenclature
| Symbol | Description |
| Effective cross-sectional area of compression member | |
| Effective weld-throat area | |
| Operational acceleration loading parameter | |
| Beta function | |
| Deformity-severity parameter | |
| Polynomial Chaos expansion coefficient | |
| E | Young’s modulus |
| Prescribed traction force | |
| Delivered traction force | |
| Allowable halo-pin load | |
| Euler buckling factor of safety | |
| Combined axial-compression and bending factor of safety | |
| Governing minimum factor of safety | |
| Halo-pin factor of safety | |
| Weld factor of safety | |
| General limit-state function | |
| Binary failure-indicator variable | |
| Weak-axis second moment of area | |
| Effective spinal stiffness surrogate | |
| Moving weight-stack mass | |
| Number of active halo pins | |
| Euler critical buckling load | |
| Probability of failure | |
| Beta probability density function | |
| Prescribed traction ratio | |
| First-order Sobol sensitivity index | |
| Total Sobol sensitivity index | |
| Treatment duration | |
| Patient body weight | |
| Total system weight | |
| Complete uncertain input vector | |
| Clinical uncertainty vector | |
| Device/manufacturing uncertainty vector | |
| Response vector | |
| Spinal elongation surrogate | |
| Beta-distribution shape parameters | |
| Pin eccentricity amplification factor | |
| Horizontal offset from the vertical-member centroid to the upper load line | |
| Pulley efficiency factor | |
| Pin load-sharing efficiency | |
| Weld-efficiency factor | |
| Average axial compressive stress | |
| Extreme-fiber combined axial and bending stress | |
| Weld shear stress | |
| Polynomial Chaos basis function | |
| Normalized uncertain variable |
References
- Taylor, M.; Bryan, R.; Galloway, F. Accounting for patient variability in finite element analysis of the intact and implanted hip and knee: A review. Int. J. Numer. Methods Biomed. Eng. 2013, 29, 273–292. [Google Scholar] [CrossRef] [PubMed]
- Falcinelli, F.; et al. Finite element analysis in implant dentistry: State of the art and future directions. J. Dent. 2023. [Google Scholar] [CrossRef] [PubMed]
- Laz, P.J.; Browne, M. A review of probabilistic analysis in orthopedic biomechanics. Proceedings of the Institution of Mechanical Engineers, Part H: Journal of Engineering in Medicine 2010, 224, 927–943. [Google Scholar] [CrossRef] [PubMed]
- Carr, I.A.; Aycock, K.I.; Paranjape, H.; Bonsignore, C.; Weaver, J.D.; Craven, B.A. Uncertainty Quantification of Finite Element Strain Predictions for a Nitinol Medical Device: Influence of Input Parameter Probability Distribution on Output Uncertainty. Cardiovasc. Eng. Technol. 2026. [Google Scholar] [CrossRef] [PubMed]
- Xiu, D.; Karniadakis, G.E. The Wiener–Askey Polynomial Chaos for Stochastic Differential Equations. SIAM J. Sci. Comput. 2002, 24, 619–644. [Google Scholar] [CrossRef]
- Xiu, D.; Lucor, D.; Su, C.H.; Karniadakis, G.E. Performance Evaluation of Generalized Polynomial Chaos. In Lecture Notes in Computer Science; Springer: Berlin, 2003; Vol. 2660, pp. 346–354. [Google Scholar]
- Thapa, M.; Mulani, S.B.; Walters, R.W. Adaptive Weighted Least-Squares Polynomial Chaos Expansion with Basis Adaptivity and Sequential Adaptive Sampling. Comput. Methods Appl. Mech. Eng. 2020, 360, 112759. [Google Scholar] [CrossRef]
- Thapa, M.; Paudel, A.; Mulani, S.B.; Walters, R.W. Uncertainty Quantification and Global Sensitivity Analysis for Progressive Failure of Fiber-Reinforced Composites. Struct. Multidiscip. Optim. 2021, 63, 245–265. [Google Scholar] [CrossRef]
- Thapa, M.; Mulani, S.B.; Paudel, A.; Gupta, S.; Walters, R.W. Classifier-Based Adaptive Polynomial Chaos Expansion for High-Dimensional Uncertainty Quantification. Comput. Methods Appl. Mech. Eng. 2024, 422, 116829. [Google Scholar] [CrossRef]
- Kantarakias, K.D.; Papadakis, G. Sensitivity-Enhanced Generalized Polynomial Chaos for Efficient Uncertainty Quantification. Comput. Methods Appl. Mech. Eng. 2023, 414, 112377. [Google Scholar] [CrossRef]
- Kantarakias, K.D.; Papadakis, G. Uncertainty Quantification of Time-Average Quantities of Chaotic Systems Using Sensitivity-Enhanced Polynomial Chaos Expansion. Phys. Rev. E 2024, 109, 044208. [Google Scholar] [CrossRef] [PubMed]
- Son, J.; Du, Y. An Efficient Polynomial Chaos Expansion Method for Uncertainty Quantification in Dynamic Systems. Appl. Mech. 2021, 2, 460–481. [Google Scholar] [CrossRef]
- Weng, Y.Y.; Liu, T.; Zhang, X.Y.; Zhao, Y.G. Probability Density Estimation of Polynomial Chaos and Its Application in Structural Reliability Analysis. Reliab. Eng. Syst. Saf. 2025, 253, 110537. [Google Scholar] [CrossRef]
- Geraci, G.; Clements, K.; Olson, A.J. A Polynomial Chaos Approach for Uncertainty Quantification of Monte Carlo Transport Codes. In Proceedings of the Proceedings of the International Conference on Mathematics and Computational Methods Applied to Nuclear Science and Engineering, 2023. [Google Scholar]
- Phillips, B.D.; Schmidt, J.; Flack, R.D.; Aretskin-Hariton, E.D. End-To-End Uncertainty Quantification with Analytical Derivatives for Design Under Uncertainty. J. Aircr. 2025, 62, 1522–1530. [Google Scholar] [CrossRef]
- Domenech, P.; Mariscal, G.; Marquina, V.; Bas, P.; Bas, T. Efficacy and Safety of Halo-Gravity Traction in the Treatment of Spinal Deformities: A Systematic Review of the Literature. Rev. Esp. De Cir. Ortop. Y Traumatol. 2024, 68, 159–167. [Google Scholar] [CrossRef] [PubMed]
- Jain, M.A.; Dhawale, A.; Iqbal, M.Z.; Naseem, A.; Sagade, B.; Gorain, A.; Nene, A. Halo Gravity Traction for Pediatric Scoliosis and Kyphoscoliosis: A Review of Current Evidence and Best Practices. World J. Orthop. 2025, 16, 110510. [Google Scholar] [CrossRef] [PubMed]
- Pratheep, G.K.; Viswanathan, V.K.; Manoharan, S.R.R. Pre-operative Halo-gravity Traction in the Treatment of Complex Spinal Deformities: What Do We Know So Far?: A Systematic Review. Indian Spine J. 2023, 6, 65–75. [Google Scholar] [CrossRef] [PubMed]
- Reed, L.A.; Mihas, A.; Butler, R.; Pratheep, G.; Manoharan, S.; Theiss, S.; Viswanathan, V. Halo Gravity Traction for the Correction of Spinal Deformities in the Pediatric Population. World Neurosurg. 2022, 164, e636–e648. [Google Scholar] [CrossRef] [PubMed]
- Yang, Z.; Liu, Y.; Qi, L.; Wu, S.; Li, J.; Wang, Y.; Jiang, B. Does Preoperative Halo-Gravity Traction Reduce Deformity and Improve Pulmonary Function? Front. Med. 2021, 8, 767238. [Google Scholar] [CrossRef] [PubMed]
- Rocos, B.; Reda, L.; Lebel, D.E.; Dodds, M.K.; Zeller, R. The Use of Halo Gravity Traction in Severe, Stiff Scoliosis. J. Pediatr. Orthop. 2021, 41, 338–343. [Google Scholar] [CrossRef] [PubMed]
- Bauer, J.M.; Yang, S.; Yaszay, B.; Mackenzie, W.G.S. Pediatric Halo Use: Indications, Application, and Potential Complications. J. Pediatr. Orthop. Soc. N. Am. 2024, 9, 100129. [Google Scholar] [CrossRef] [PubMed]
- Wang, J.H.; Daniels, A.H.; Palumbo, M.A.; Eberson, C.P. Cervical Traction for the Treatment of Spinal Injury and Deformity. JBJS Rev. 2014, 2, e4. [Google Scholar] [CrossRef] [PubMed]
- Li, G.; Compson, K.; Stone, J.D.; Sanders, J.O.; Louer, C.R. Pathway for Implementation of Halo-Gravity Traction for the Treatment of Severe Spinal Deformities at a New Institution. J. Pediatr. Orthop. Soc. N. Am. 2021, 3, 1–20. [Google Scholar] [CrossRef]
Figure 1.
Fabricated prototype and corresponding CAD representation of the proposed halo-gravity traction wheelchair support system.
Figure 1.
Fabricated prototype and corresponding CAD representation of the proposed halo-gravity traction wheelchair support system.

Figure 2.
Probability-density distribution of the governing minimum factor of safety obtained from the uncertainty-propagation framework.
Figure 2.
Probability-density distribution of the governing minimum factor of safety obtained from the uncertainty-propagation framework.
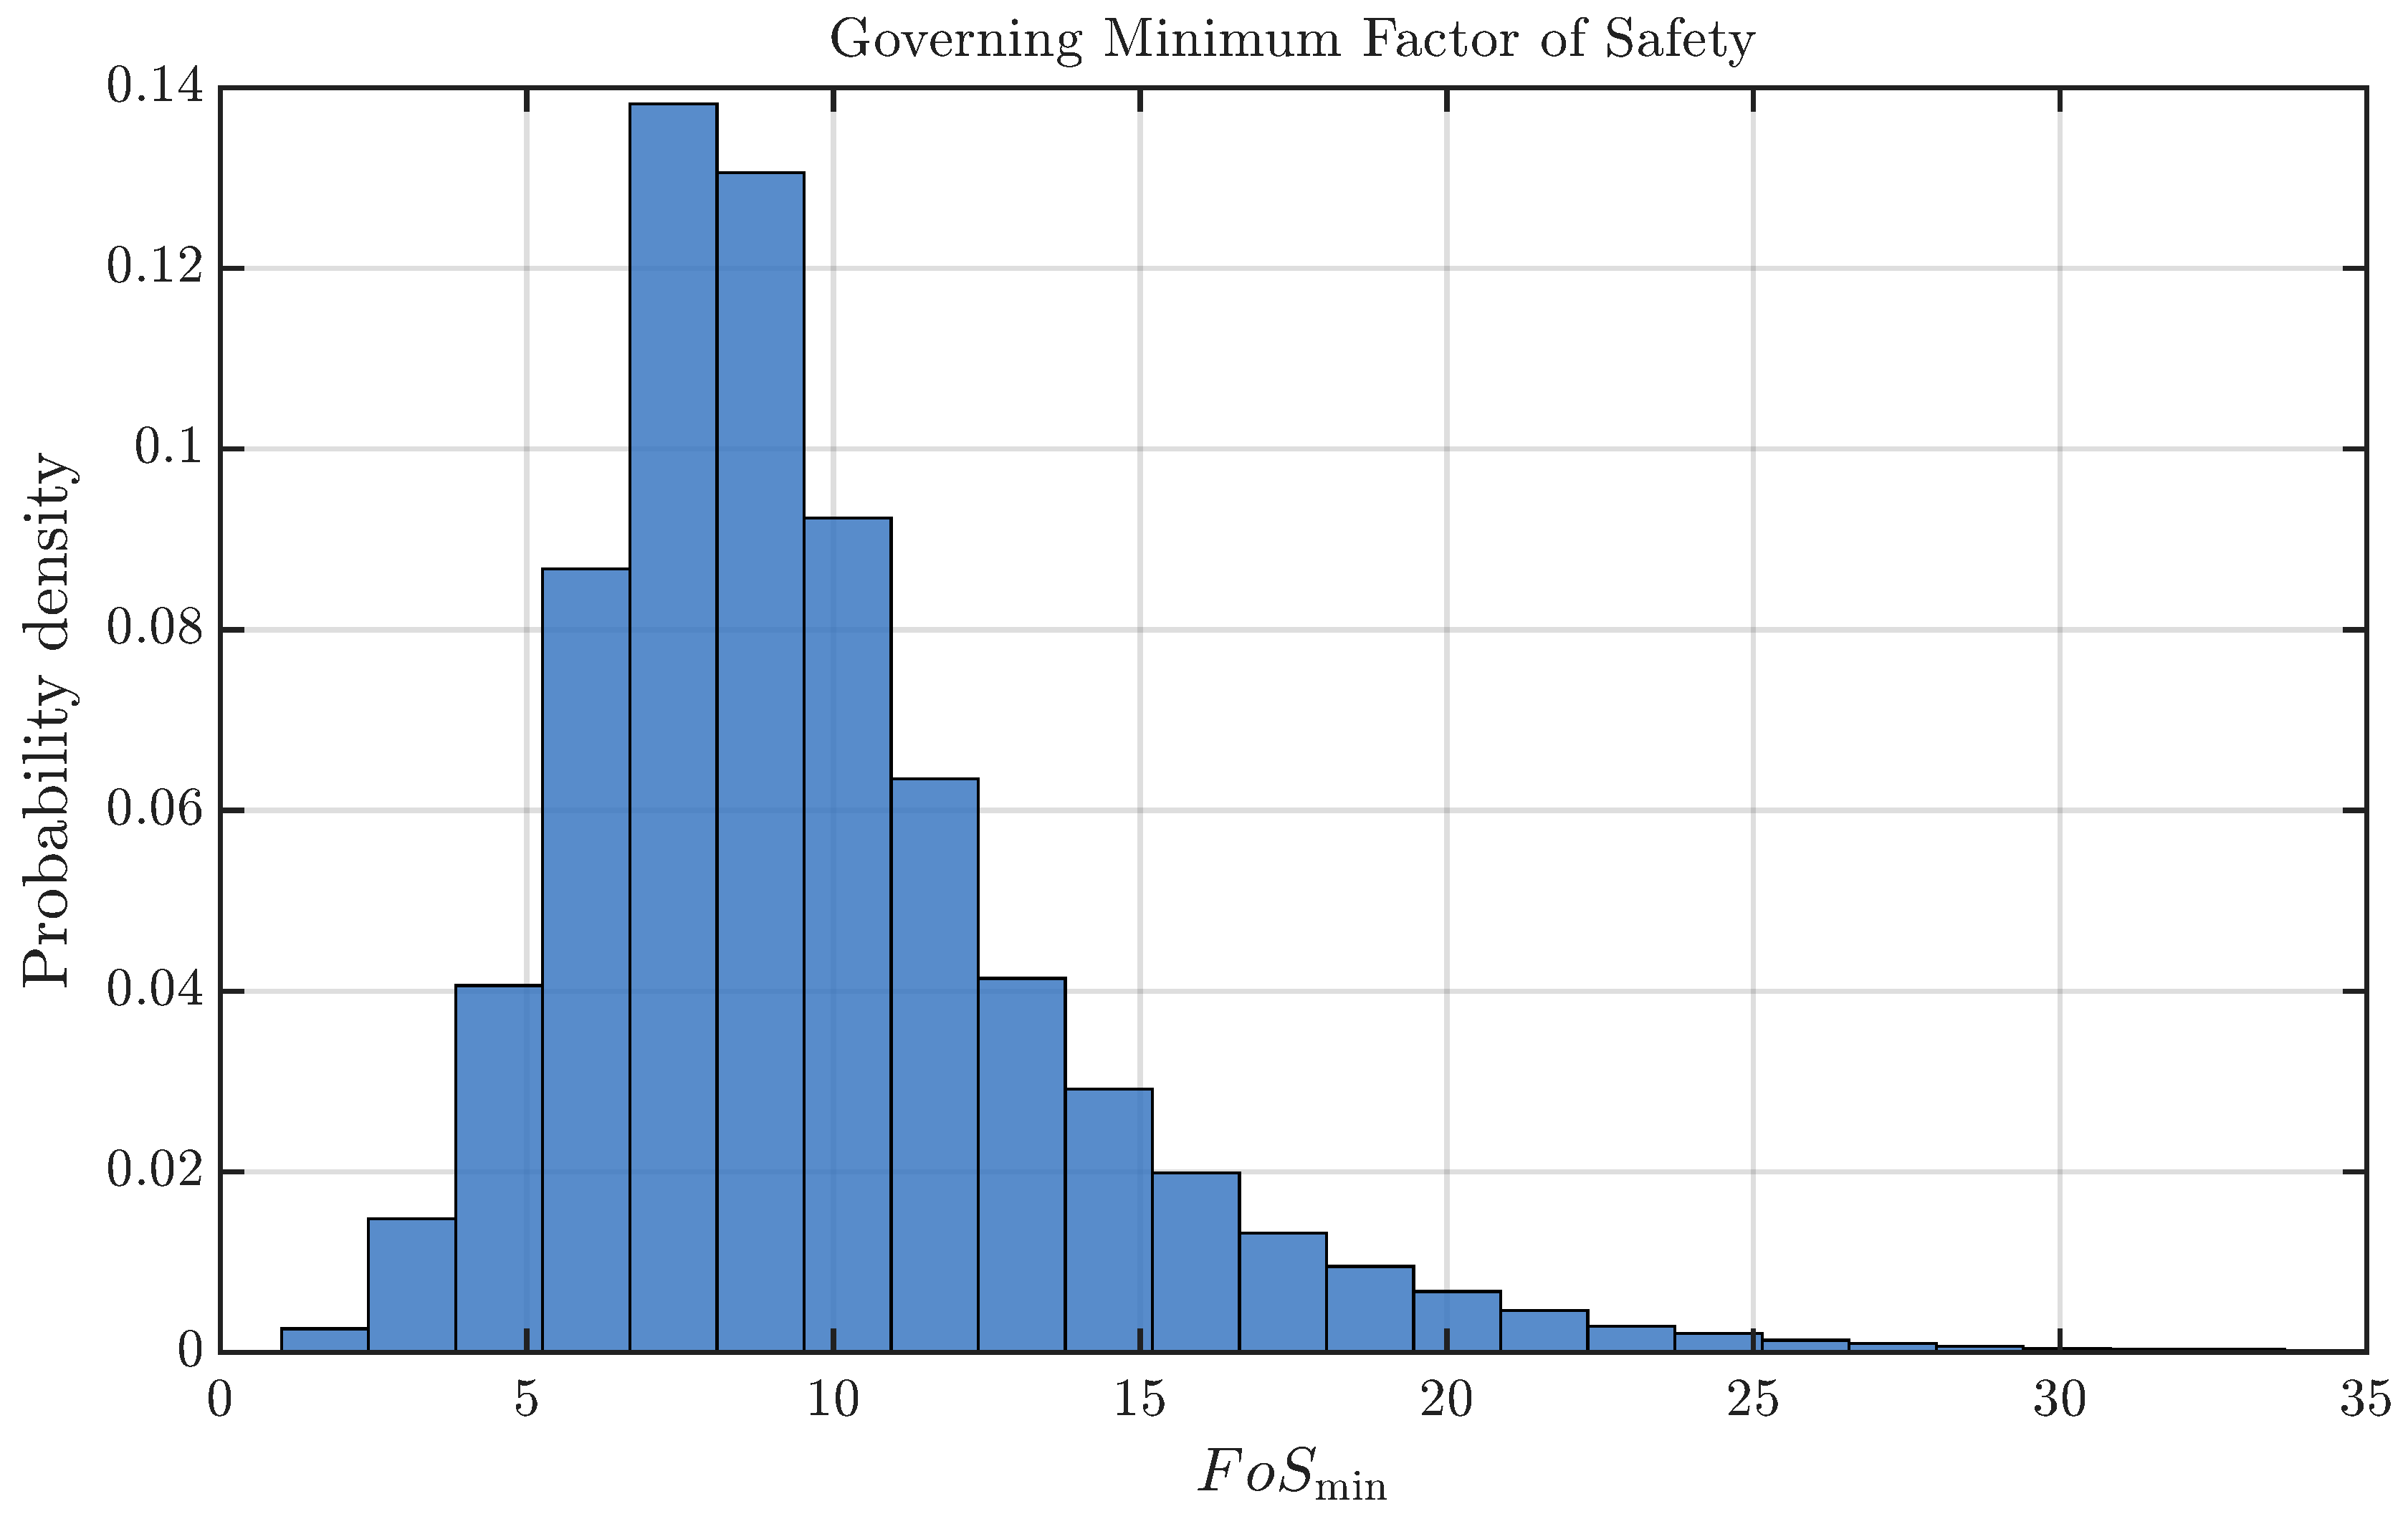
Figure 3.
Screening Sobol-like sensitivity indices for the governing minimum factor of safety.
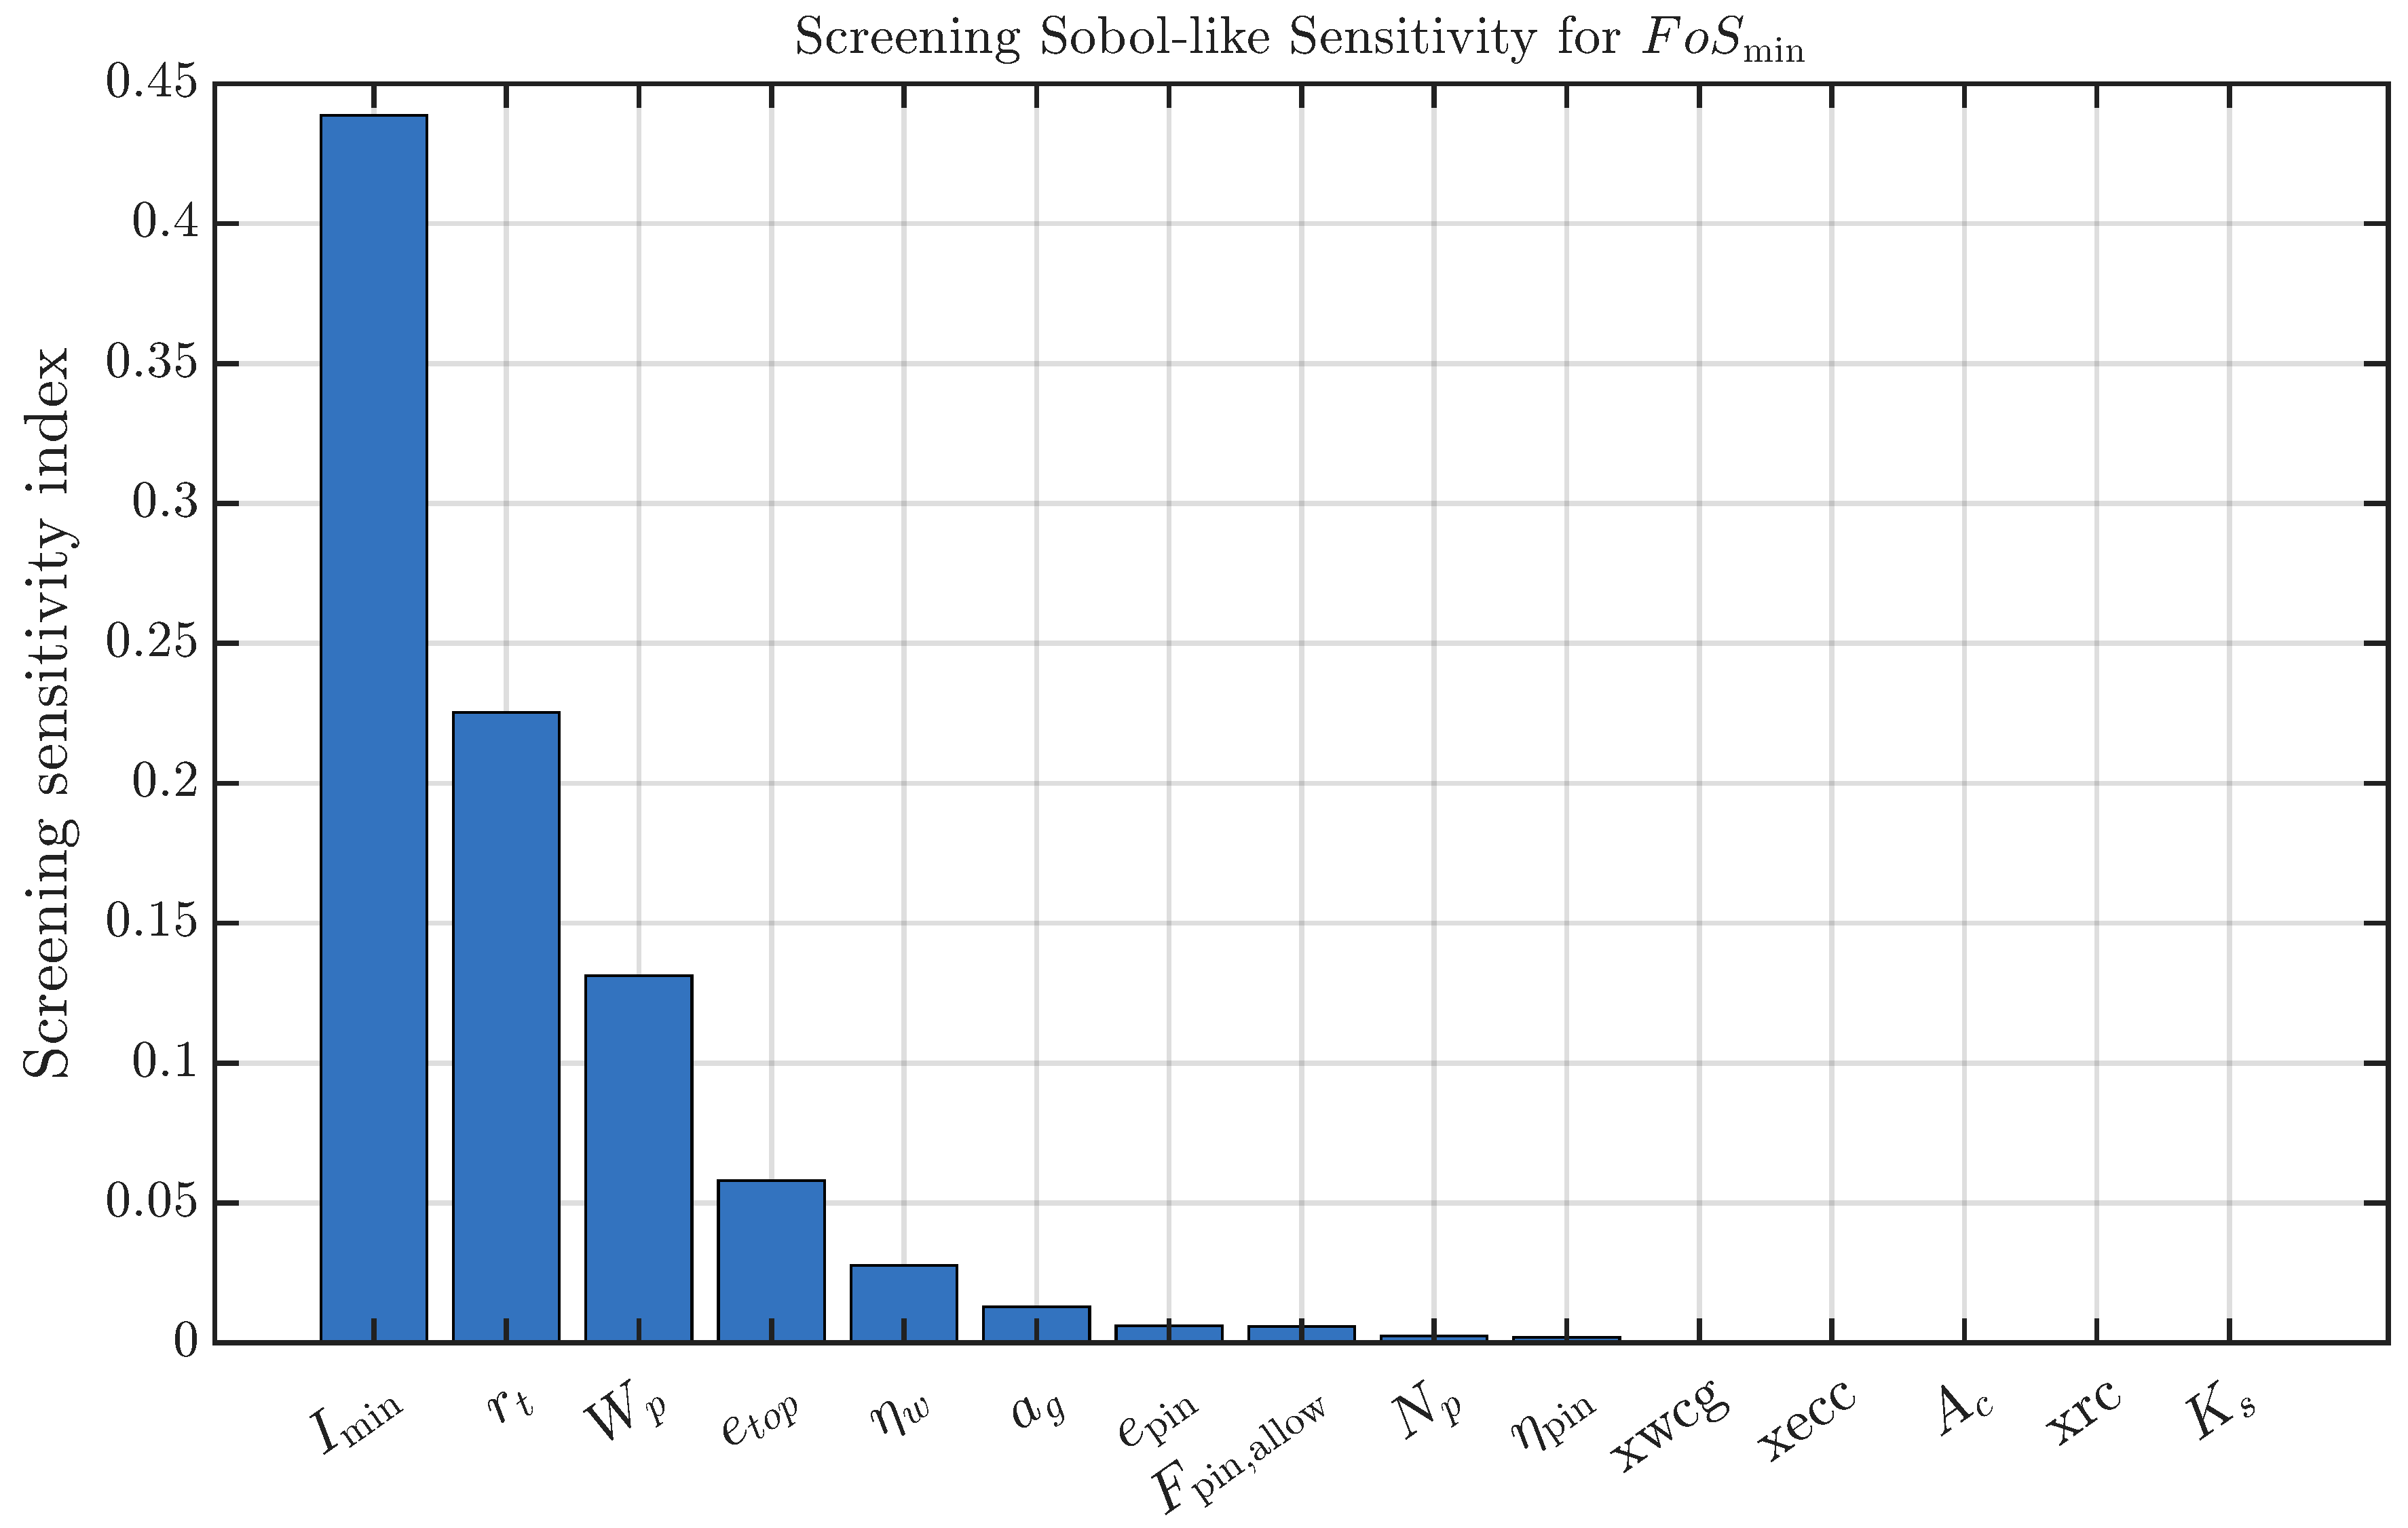
Figure 4.
Probability-density distribution of the halo-pin factor of safety.
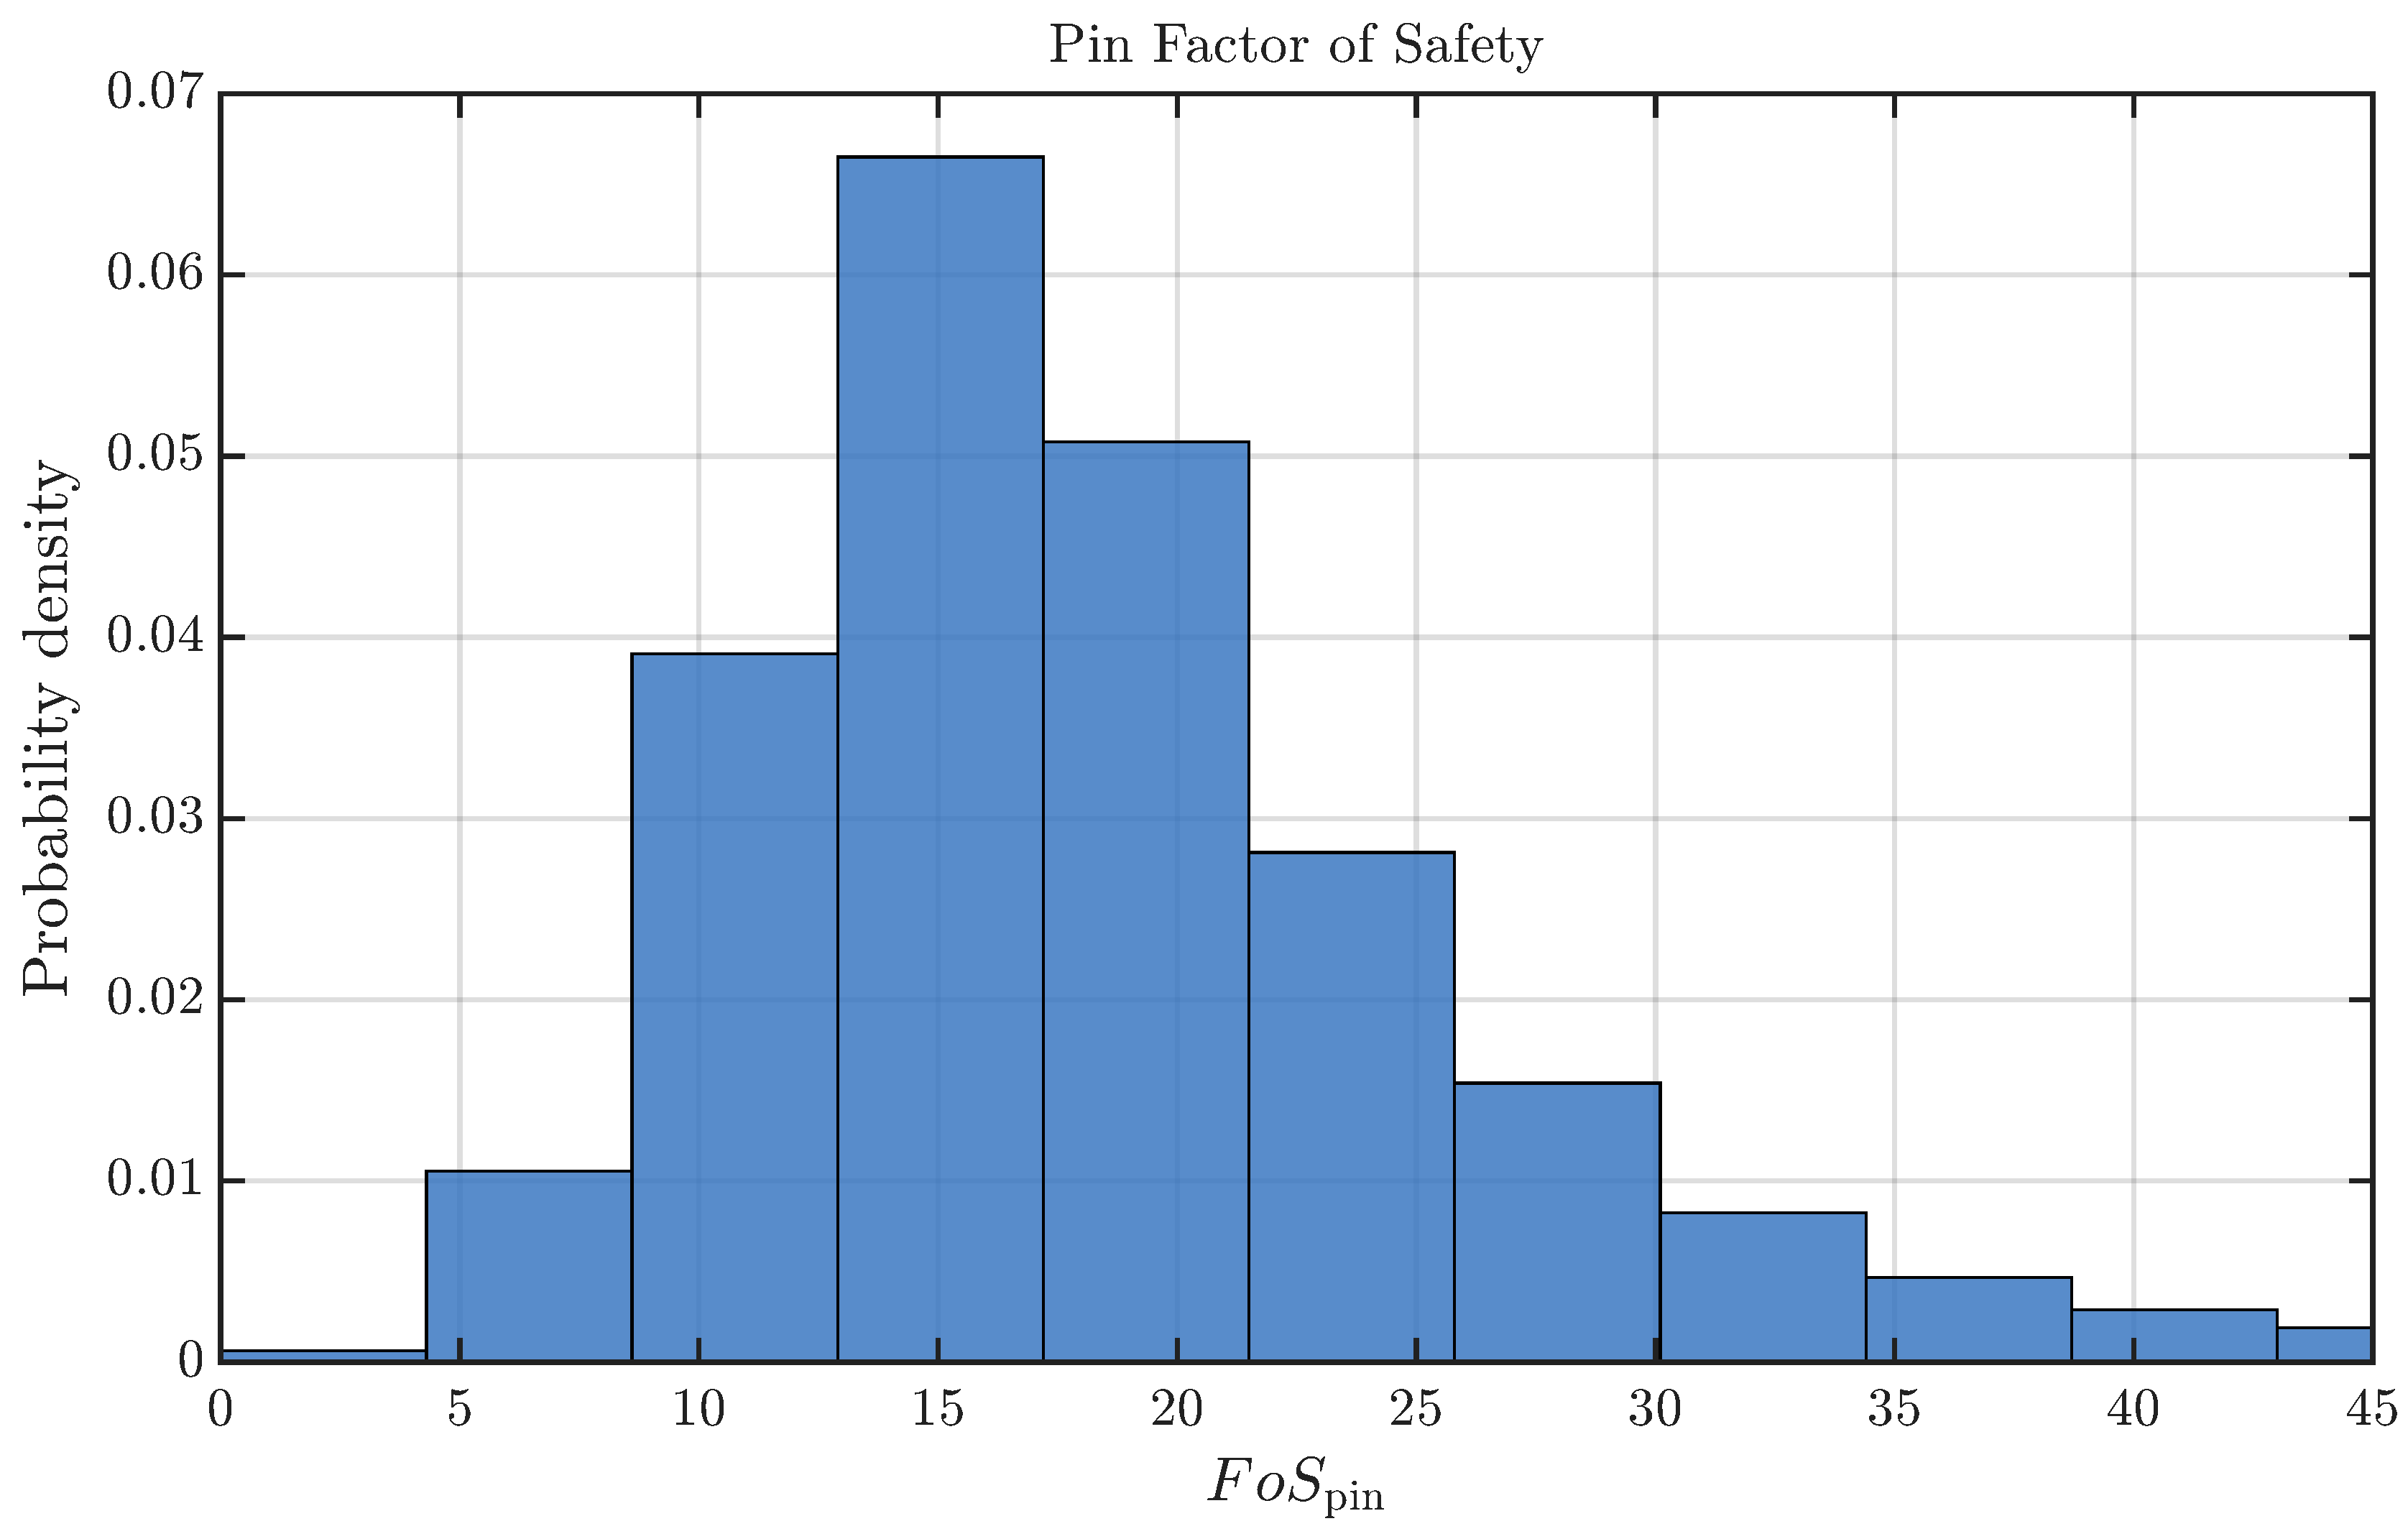
Figure 5.
Governing structural-mode distribution obtained from the uncertainty-propagation framework.
Figure 5.
Governing structural-mode distribution obtained from the uncertainty-propagation framework.
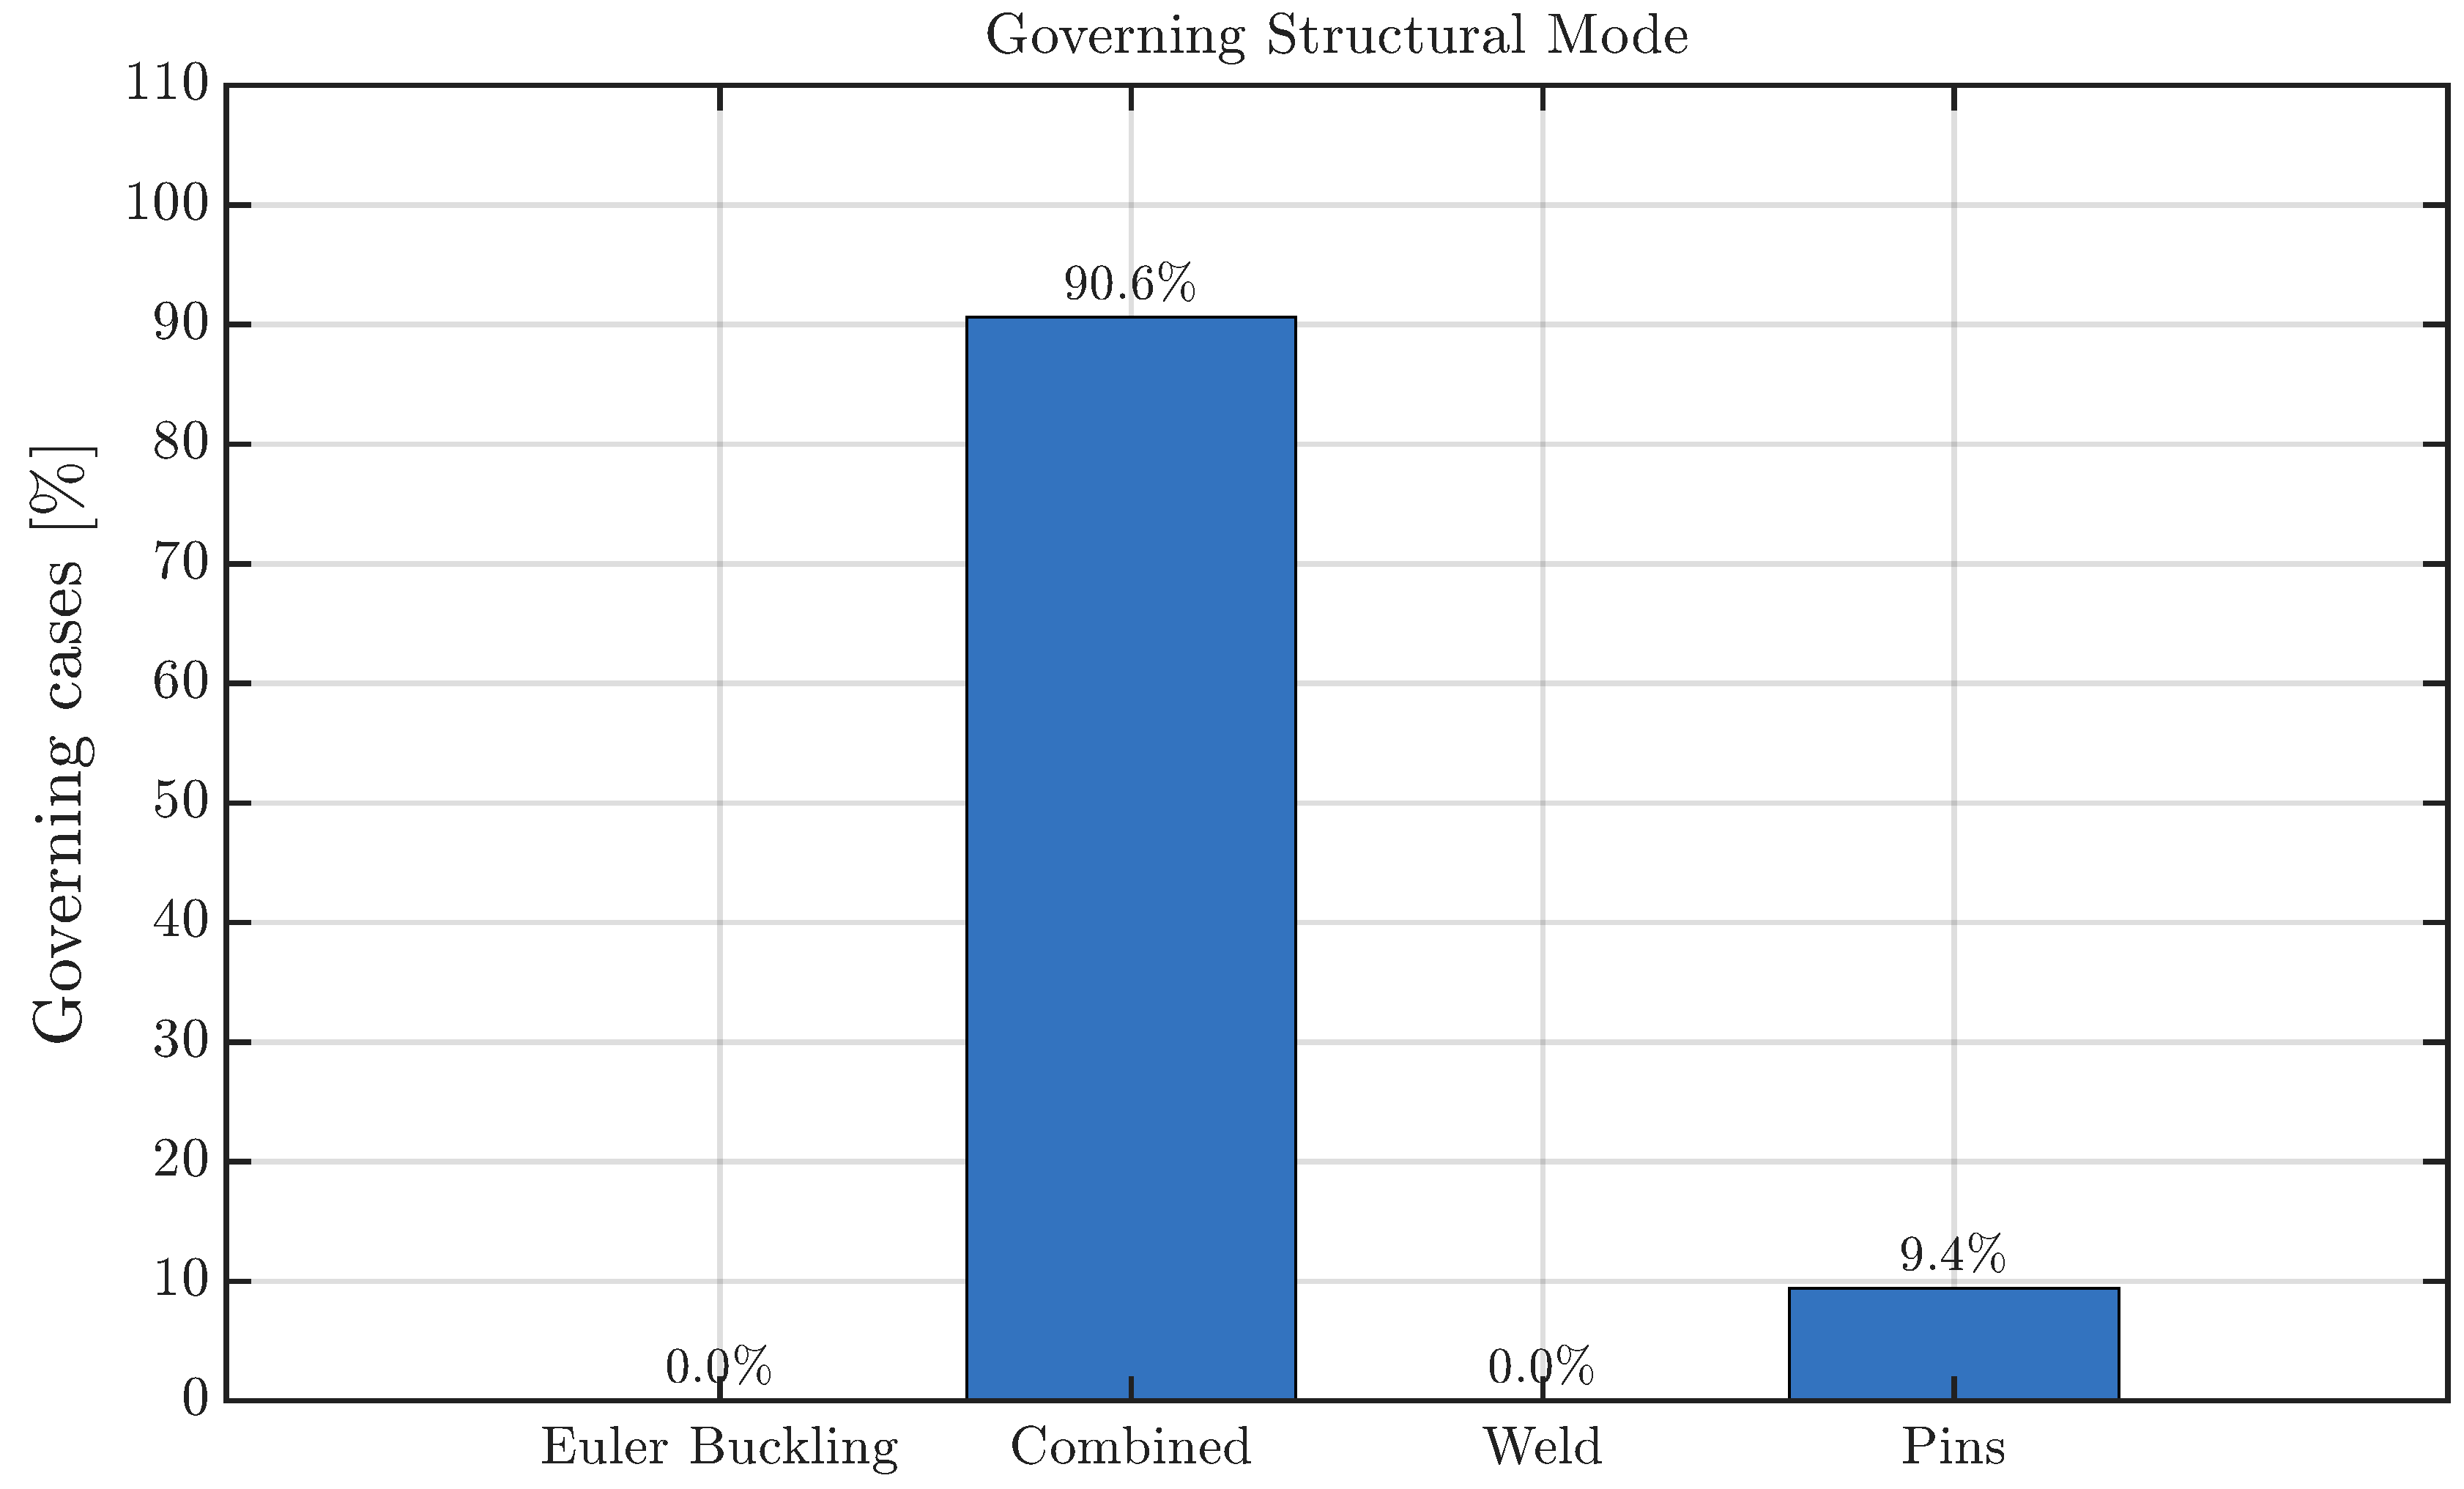
Figure 6.
Probability-density distribution of the delivered traction force.
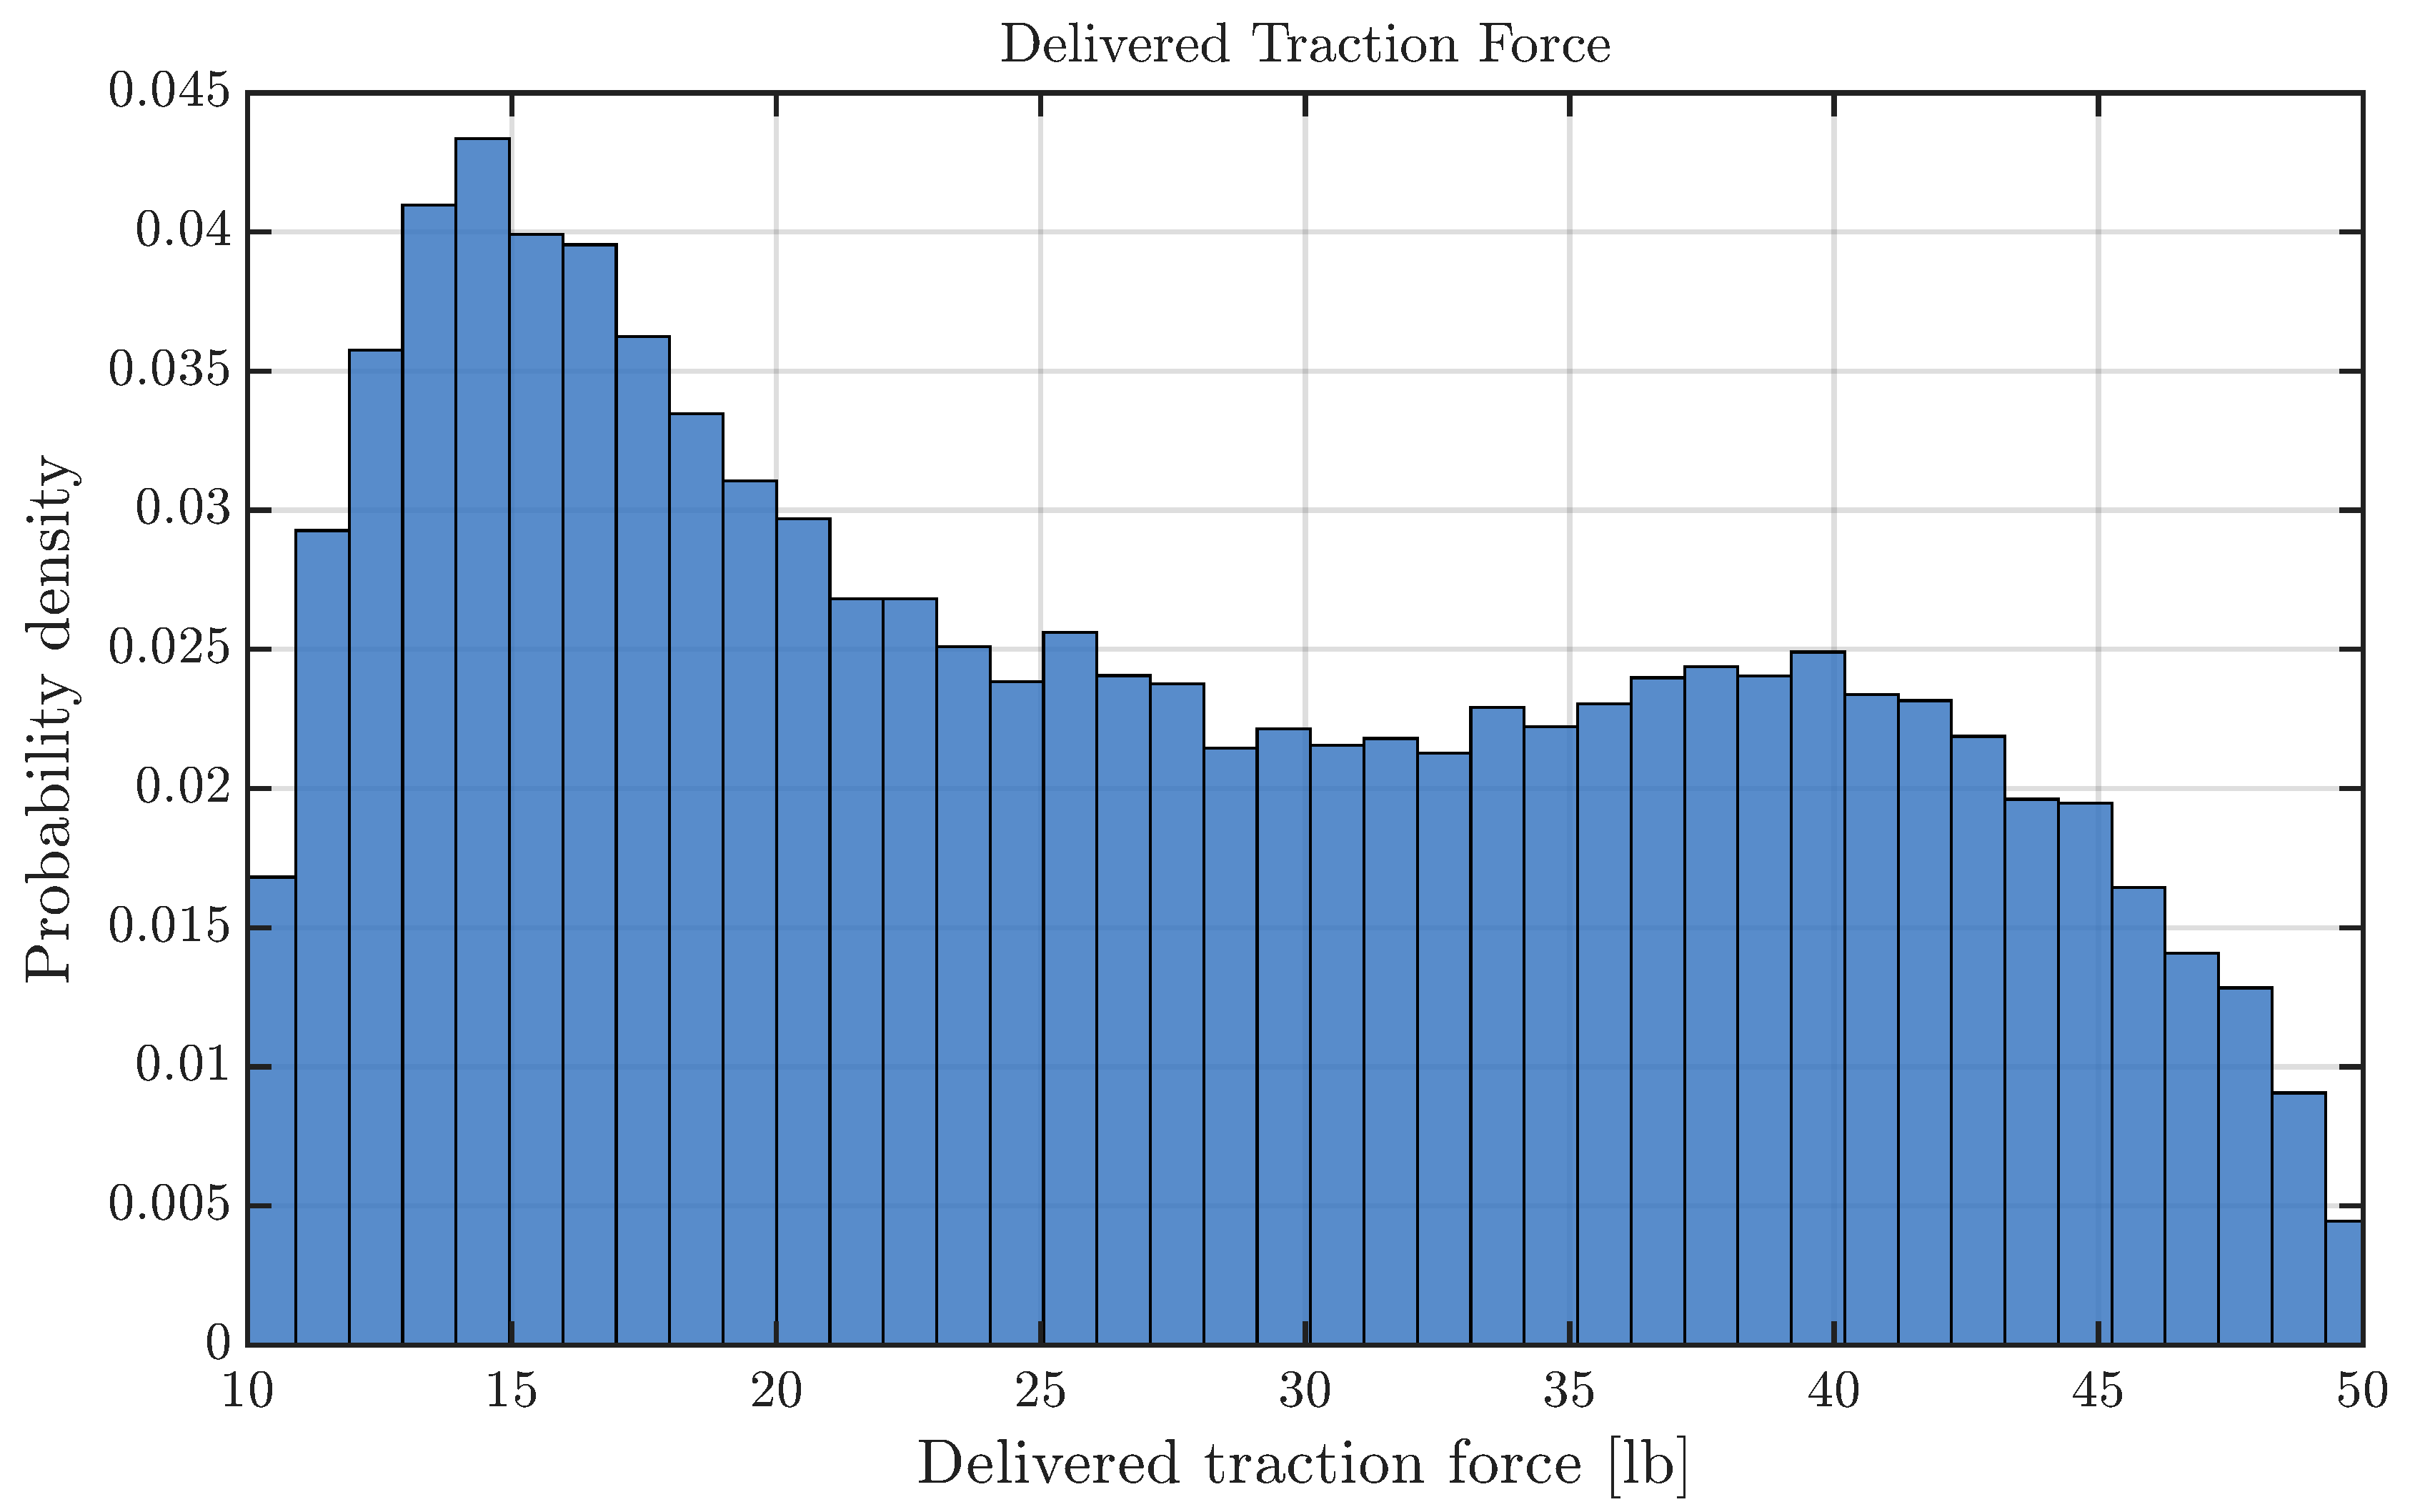
Figure 7.
Probability-density distribution of the clinical surrogate response parameter.
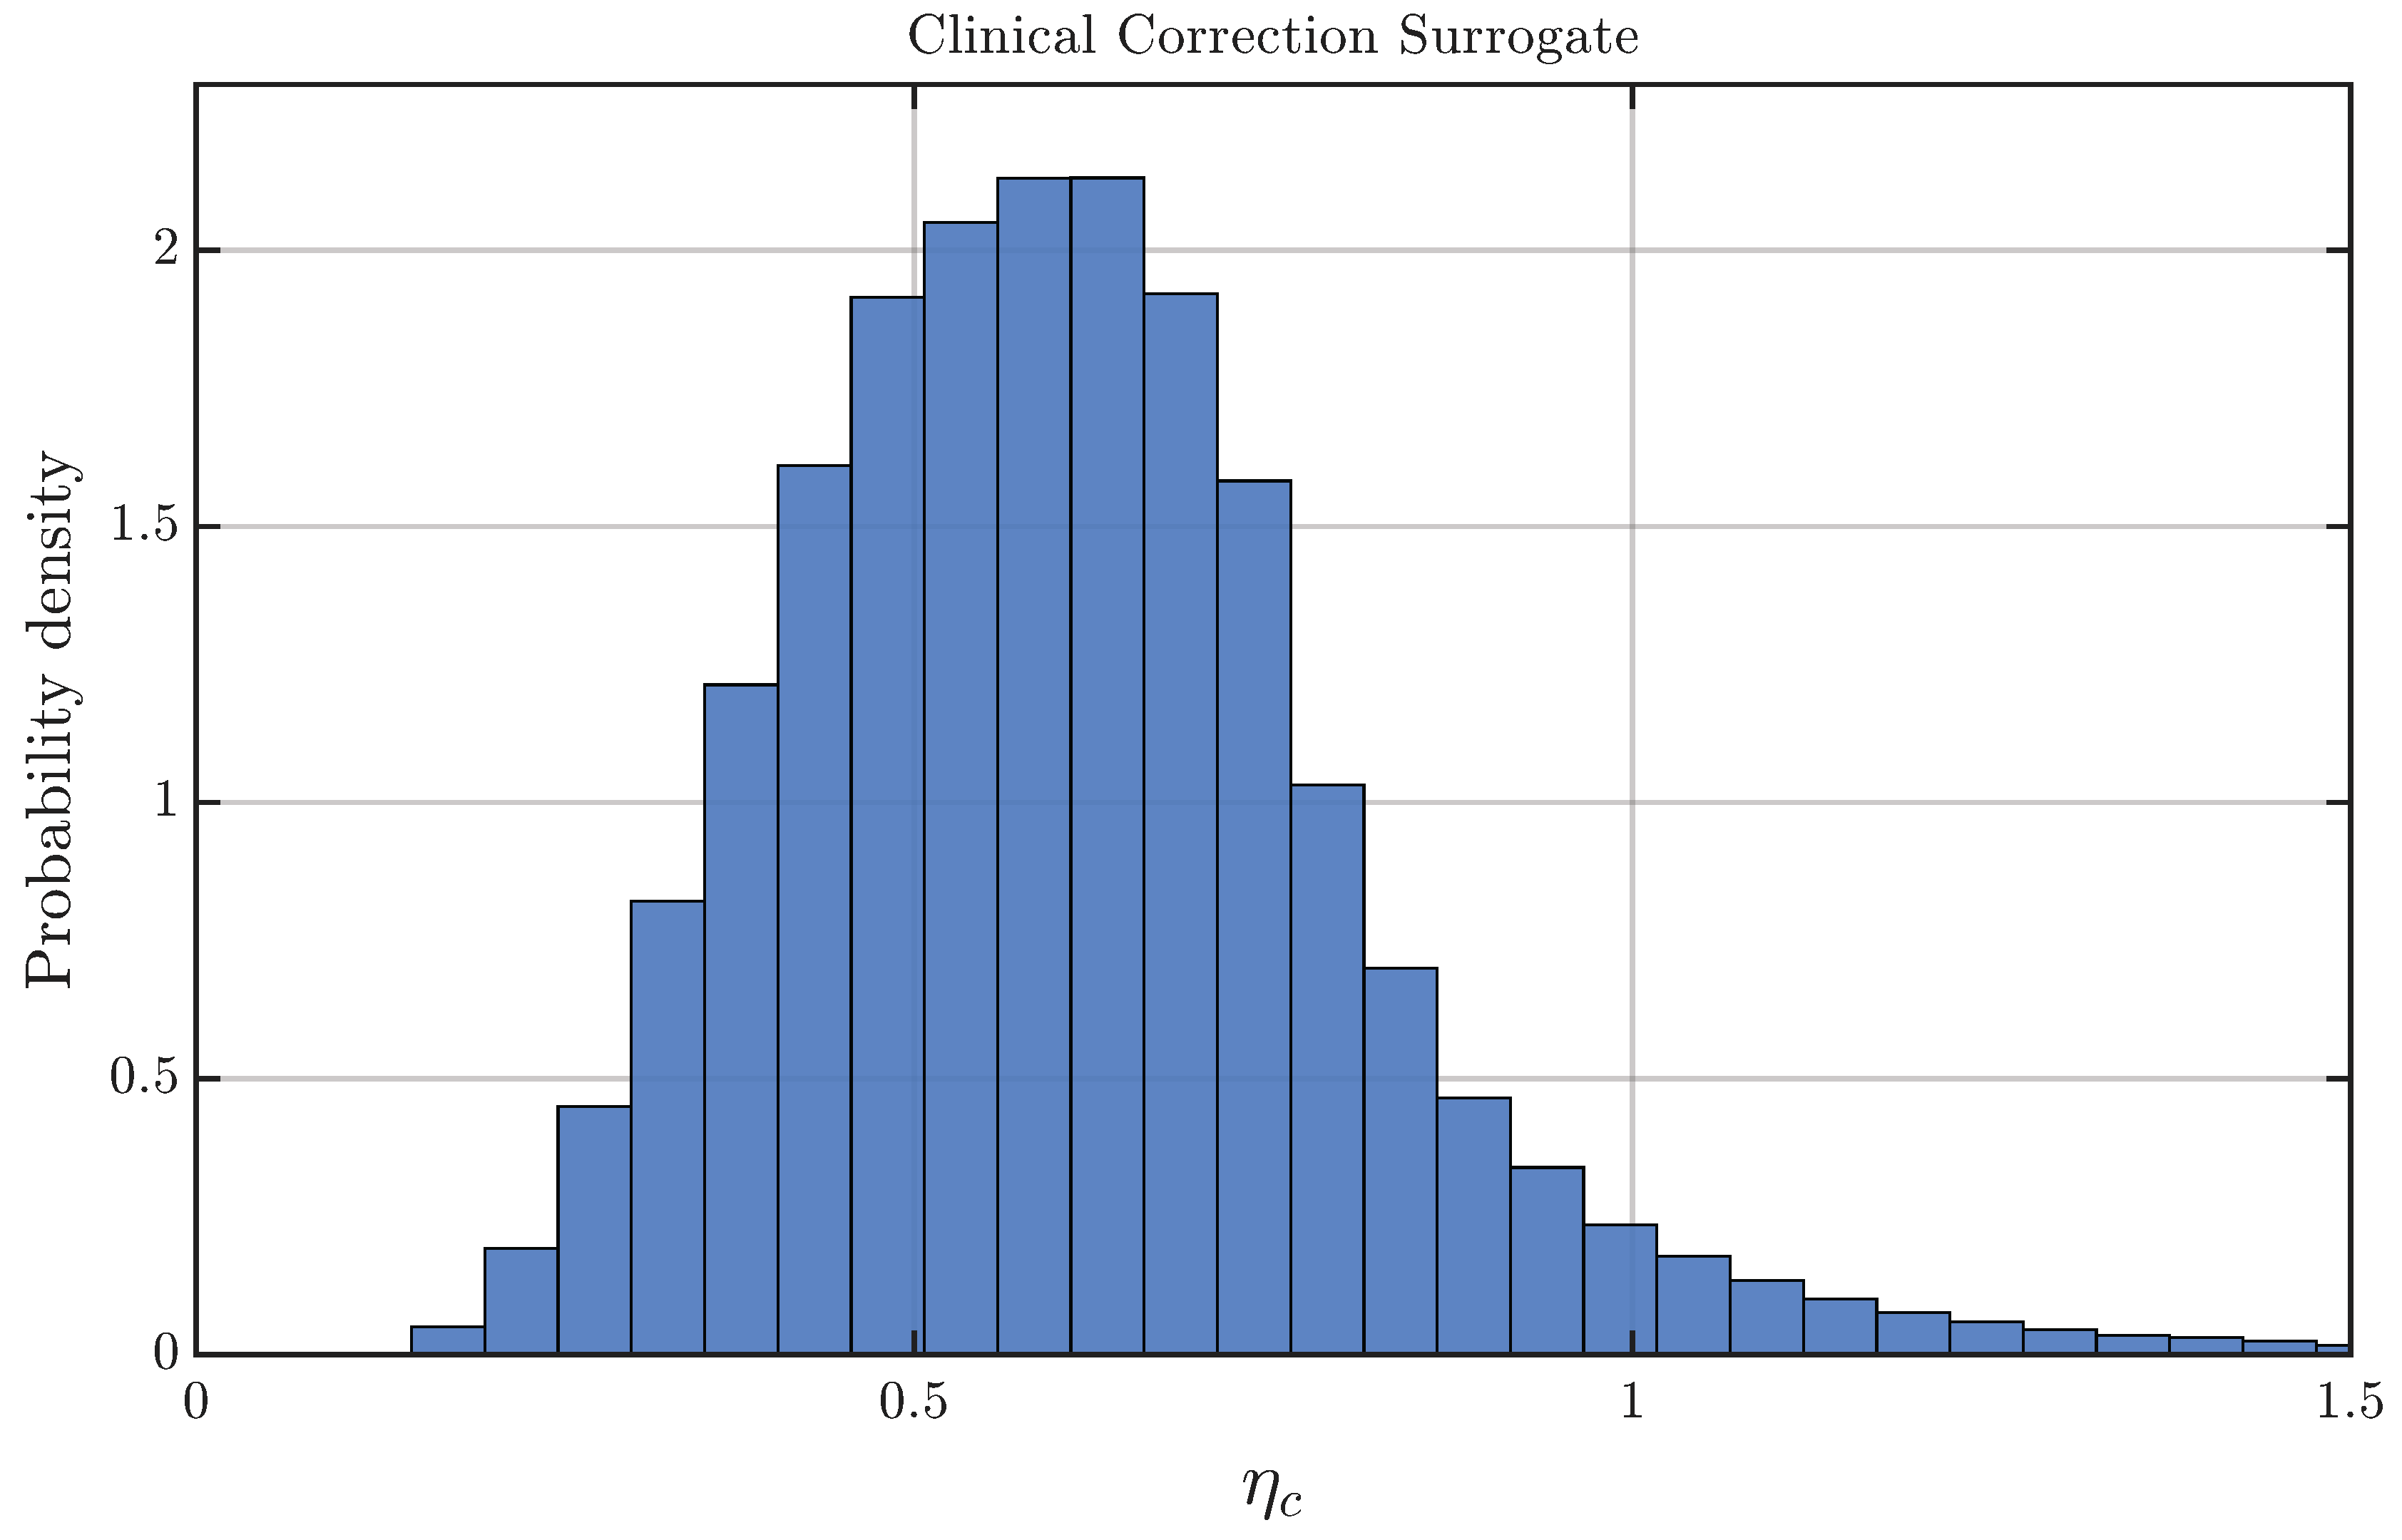

Table 1.
Representative uncertain input variables and bounded beta-distribution ranges used in the coupled clinical–structural uncertainty quantification framework.
Table 1.
Representative uncertain input variables and bounded beta-distribution ranges used in the coupled clinical–structural uncertainty quantification framework.
| Variable | Description | Lower | Upper |
|---|---|---|---|
| Patient body weight [lb] | 50 | 100 | |
| Traction-load ratio | 0.20 | 0.50 | |
| Effective spinal stiffness surrogate [lb/in] | 15 | 45 | |
| Number of active halo pins | 4 | 8 | |
| Allowable halo-pin load [lb] | 100 | 300 | |
| Pin-load eccentricity amplification factor | 1.0 | 3.0 | |
| Halo-pin load-sharing efficiency | 0.50 | 1.00 | |
| Vertical support cross-sectional area [in2] | 1.0 | 1.8 | |
| Weak-axis second moment of area [in4] | 0.05 | 0.25 | |
| Load eccentricity of upper support arm [in] | 12 | 20 | |
| Weld/fabrication efficiency factor | 0.70 | 1.00 | |
| Rear caster support location [in] | 18 | 30 | |
| Weight-stack center-of-gravity location [in] | 12 | 23 | |
| Traction-line eccentricity [in] | 0.5 | 4.0 | |
| Operational acceleration [g] | 0.00 | 0.25 |
Table 2.
Summary statistics obtained from the coupled clinical–structural uncertainty quantification framework.
Table 2.
Summary statistics obtained from the coupled clinical–structural uncertainty quantification framework.
| Response | Mean | P05 | P50 | P95 |
|---|---|---|---|---|
| 9.67 | 4.60 | 8.81 | 17.57 | |
| 10.03 | 4.68 | 8.94 | 18.00 | |
| 19.08 | 8.69 | 17.17 | 35.52 | |
| 81.28 | 39.87 | 73.78 | 147.52 | |
| 140.35 | 70.90 | 123.94 | 258.13 | |
| [lb] | 27.09 | 12.02 | 25.69 | 45.67 |
| 0.61 | 0.32 | 0.59 | 0.97 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.