
Submitted:
03 September 2026
Posted:
13 September 2026
You are already at the latest version
Abstract
Background and Objectives: Consolidation durvalumab after chemoradiotherapy (CRT) is the standard of care for unresectable stage III non-small cell lung cancer (NSCLC). However, a substantial proportion of patients do not receive this treatment in real-world practice.. This study aimed to evaluate the efficacy of post-progression immune checkpoint inhibitor (ICI) therapy in patients with stage III NSCLC who did not receive durvalumab consolidation. Materials and Methods: This multicenter retrospective study included 403 patients with stage III NSCLC who received definitive CRT without durvalumab consolidation between January 2010 and December 2025. Patients were divided into ICI group (n=61) and non-ICI group (n=338) based on post-progression treatment. All patients has ECOG PS 0-1 The primary endpoint was overall survival (OS), analyzed using Kaplan-Meier and multivariate Cox regression methods. Early progression was defined as recurrence within 6 months after CRT completion. Results: The median OS was significantly longer in the ICI group compared to the non-ICI group (47.97 months [95% CI: 35.68–60.26] vs. 19.29 months [95% CI: 17.88–20.69]; p<0.001), representing a 2.5-fold survival advantage. Patients with early progression had a significantly worse prognosis compared to those with late progression (median OS: 7.06 vs. 20.01 months; p<0.001). In the ICI group, PD-L1-positive patients had numerically longer median OS than PD-L1-negative patients (54.05 vs. 46.03 months). Multivariate analysis identified post-progression ICI use (HR: 0.37, 95% CI: 0.25–0.54; p<0.001) and early progression (HR: 2.61, 95% CI: 1.91–3.57; p<0.001) as independent prognostic factors. Conclusions: Post-progression immunotherapy was associated witha significant survival benefit in patients with stage III NSCLC who did not receive durvalumab consolidation, with a median OS approaching 48 months. Early progression within 6 months after CRT is the strongest negative prognostic factor. These findings suggest that immunotherapy should be considered in this frequently encountered patient population, provided performance status is adequate. Prospective validation is needed.
Keywords:
stage III non-small cell lung cancer
; durvalumab
; immunotherapy
; post-progression treatment
; overall survival
1. Introduction
Non-small cell lung cancer (NSCLC) remains the leading cause of cancer-related mortality worldwide. Approximately one-third of all NSCLC cases present with stage III disease, which exhibits a highly heterogeneous clinical spectrum [1,2]. For many years, platinum-based concurrent chemoradiotherapy (CRT) was the standard treatment for unresectable stage III NSCLC. However, even with this approach, median progression-free survival (PFS) was approximately 8 months, and 5-year overall survival (OS) rates remained as low as 15–30% [3,4].
The PACIFIC trial represented a paradigm shift in this field. It demonstrated that consolidation durvalumab after definitive CRT significantly improved median OS from 29.1 months to 47.5 months compared to placebo [5,6]. Consequently, 12 months of durvalumab consolidation therapy after CRT became the standard of care for unresectable stage III NSCLC.
In subsequent years, the findings of the PACIFIC trial have been corroborated by numerous real-world studies [7,8,9]. Similarly, the Brazilian LACOG 0120 study reported a median OS of 34.9 months, confirming the reproducibility of PACIFIC results in real-world settings [8]. However, real-world studies have also revealed that durvalumab utilization rates remain below expectations. A US-based study reported that only 61.5% of eligible patients received durvalumab consolidation after CRT, while 38.5% were managed with observation alone [10].
Even among patients receiving durvalumab consolidation, progression during or after treatment remains a significant challenge. Approximately 50% of patients in the PACIFIC trial progressed within 12–18 months after initiating durvalumab [5,6]. Post-progression treatment strategies have become an increasingly prominent focus in the literature. In a 23-center Italian study, platinum-based chemotherapy (43.0%) was the most commonly used treatment after durvalumab progression; however, the best survival outcomes were observed in patients receiving immunotherapy rechallenge. [11].
A notable gap exists in the literature regarding patients who do not receive durvalumab consolidation. This patient population comprises individuals who, for various reasons (early progression, deterioration in performance status, comorbidities, access issues, physician preference, etc.), did not receive the current standard of care and were followed with observation alone after CRT. Whether these patients benefit from immunotherapy (nivolumab, pembrolizumab, etc.) when they progress during follow-up remains insufficiently investigated.
In this study, we aimed to evaluate the efficacy of immunotherapy administered upon progression in patients with unresectable stage III NSCLC who did not receive durvalumab consolidation after definitive CRT. Our primary objective was to investigate the impact of post-progression immunotherapy on overall survival. Secondary objectives included the analysis of factors influencing immunotherapy response and identification of prognostic factors.
2. Materials and Methods
2.1. Study Design and Patients
This study is a multicenter, retrospective cohort study evaluating the efficacy of post-progression immune checkpoint inhibitor (ICI) therapy in patients with unresectable stage III non-small cell lung cancer (NSCLC) who received definitive chemoradiotherapy (CRT) without subsequent durvalumab consolidation. A total of 403 patients who presented to oncology clinics between January 2010 and December 2025 were included. Patients were divided into two groups based on post-progression treatment: ICI recipients (n=61) and non-ICI recipients (n=338).
Inclusion criteria: Histopathologically confirmed stage III NSCLC, receipt of definitive CRT, no durvalumab consolidation after CRT, and radiological progression during follow-up and ECOG performance status 0-1 at both diagnosis and progression.
Exclusion criteria: Stage IV disease, presence of driver mutations (EGFR, ALK, ROS1, etc.), active autoimmune disease, or absolute contraindications to immunotherapy or ECOG PS≥2.
Rationale for ICI non-receipt: During the study period, the reimbursement status of immune checkpoint inhibitors for stage III NSCLC in Turkiye changed over time. Immune checkpoint inhibitors (nivolumab and pembrolizumab) were not reimbursed by the Social Security Institution (SGK) for the post-progression setting in stage III NSCLC until July 2025. Consequently, all patients who progressed before July 2025 (n=338) did not receive ICI due to lack of reimbursement and limited access, whereas patients who progressed after July 2025 (n=61) were able to receive ICI through the national reimbursement system. This temporal difference in treatment allocation reflects the change in national health policy rather than differences in patient characteristics, performance status, or disease burden. All patients in both groups had ECOG PS 0–1 at the time of progression, and no other clinical or demographic factors influenced the decision to administer ICI. Therefore, the comparison between the ICI and non-ICI groups is based on a natural experiment of policy change, minimizing the risk of selection bias.
Post-progression immunotherapy agents were nivolumab or pembrolizumab, administered at standard doses (nivolumab 240 mg every 2 weeks or 480 mg every 4 weeks; pembrolizumab 200 mg every 3 weeks). Treatment responses were evaluated according to RECIST 1.1 criteria. Progression was defined as radiologically confirmed disease progression from the date of CRT completion. Early progression was defined as progression occurring within the first 6 months after CRT.
2.2. Statistical Analysis
Statistical analyses were performed using SPSS version 20.0 (IBM Corp., Armonk, NY, USA). Categorical variables were summarized as frequencies and percentages, while continuous variables were presented as mean ± standard deviation or median (IQR). Group comparisons were performed using the Chi-square or Fisher’s exact test for categorical variables and the Student’s t-test or Mann-Whitney U test for continuous variables.
Survival analyses were conducted using the Kaplan-Meier method, with group comparisons performed using the log-rank test. Overall survival (OS) was defined as the time from documented disease progression to death or last follow-up. The time from CRT completion to progression was used only to define early progression (≤6 months).
Variables found to be significant in univariate analysis(p<0.10) were included in multivariate Cox regression analysis. All statistical tests were two-sided, with p<0.05 considered statistically significant.
3. Results
3.1. Patient Demographics and Clinical Characteristics
A total of 403 patients were included in the study. All patients (n=403, 100%) did not receive durvalumab consolidation after CRT and developed progression during follow-up. Post-progression 61 patients (15.1%) received immunotherapy (ICI), while 338 patients (83.9%) did not.All patients had ECOG performance status 0–1. Demographic and clinical characteristics of the patients are summarized in Table 1.

Table 1.
Demographic and Clinical Characteristics of Patients.
| Characteristic | ICI Group (n=61) | Non-ICI Group (n=338) | Total (n=403) | p-value |
| Sex, n (%) | 0.621 | |||
| Male | 59 (96.7) | 322 (95.3) | 381 (94.5) | |
| Female | 2 (3.3) | 16 (4.7) | 18 (4.5) | |
| Age, years (median, IQR) | 65.18 (60.2–70.1) | 65.27 (59.8–71.0) | 65.25 (60.0–70.8) | 0.872 |
| ECOG PS, n (%) | 1.000 | |||
| 0–1 | 61 (100) | 338 (100) | 403 (100) | |
| Histology, n (%) | 0.031 | |||
| Squamous | 40 (65.6) | 265 (78.4) | 305 (75.7) | |
| Non-squamous | 21 (34.4) | 73 (21.6) | 94 (23.3) | |
| Stage III substage, n (%) | 0.412 | |||
| IIIA | 27 (44.3) | 168 (49.7) | 195 (48.4) | |
| IIIB | 23 (37.7) | 115 (34.0) | 138 (34.2) | |
| IIIC | 11 (18.0) | 55 (16.3) | 66 (16.4) | |
| PD-L1 status, n (%) | <0.001 | |||
| Negative | 19 (31.1) | 22 (6.5) | 41 (10.2) | |
| Positive | 31 (50.8) | 19 (5.6) | 50 (12.4) | |
| Not available | 11 (18.0) | 297 (87.9) | 312 (77.4) | |
| PD-L1 categorical, n (%) | <0.001 | |||
| Negative | 19 (31.1) | 22 (6.5) | 41 (10.2) | |
| 1–50% | 20 (32.8) | 9 (2.7) | 29 (7.2) | |
| >50% | 11 (18.0) | 10 (3.0) | 21 (5.2) | |
| Not available | 11 (18.0) | 297 (87.9) | 312 (77.4) | |
| T-stage, n (%) | 0.134 | |||
| T1 | 1 (1.6) | 27 (8.0) | 28 (6.9) | |
| T2 | 22 (36.1) | 118 (34.9) | 140 (34.7) | |
| T3 | 17 (27.9) | 118 (34.9) | 135 (33.5) | |
| T4 | 21 (34.4) | 74 (21.9) | 95 (23.6) | |
| N-stage, n (%) | 0.693 | |||
| N0 | 5 (8.2) | 43 (12.7) | 48 (11.9) | |
| N1 | 5 (8.2) | 38 (11.2) | 43 (10.7) | |
| N2 | 43 (70.5) | 205 (60.7) | 248 (61.5) | |
| N3 | 8 (13.1) | 50 (14.8) | 58 (14.4) | |
| Early progression (≤6 months), n (%) | 0.001 | |||
| Yes | 19 (31.1) | 182 (53.8) | 201 (49.9) | |
| No | 41 (67.2) | 156 (46.2) | 197 (48.9) |
Abbreviations: ICI, immune checkpoint inhibitor; PS, performance status; IQR, interquartile range. p-values calculated using Chi-square or Fisher’s exact test for categorical variables, Mann-Whitney U test for continuous variables. Statistically significant values (p<0.05) are shown in bold.
3.2. Overall Survival (OS) Analyses
3.2.1. Effect of Post-Progression ICI Use on OS
Patients who received post-progression ICI had a median OS of 47.967 months (95% CI: 35.678–60.256), compared to 19.285 months (95% CI: 17.883–20.687) in the non-ICI group (p<0.001, log-rank test). The survival benefit in the ICI group was 2.5-fold (Figure 1).
3.2.2. Effect of Early Progression on OS
Patients who progressed within the first 6 months after CRT had a median OS of 7.064 months, compared to 20.008 months for patients who progressed after 6 months (p<0.001) (Figure 2). Early progression emerged as a strong negative prognostic factor in the entire cohort. Due to the small sample size in the early progression ICI subgroup (n=19), further stratification by ICI use was not performed.
3.2.3. PD-L1 Status and OS
Among patients who received post-progression ICI, PD-L1 positive patients had a median OS of 54.045 months (95% CI: 31.849–76.241), while PD-L1 negative patients had a median OS of 46.029 months (95% CI: 35.678–56.380).
In the non-ICI group, PD-L1 positive patients had an OS of 12.189 months, and PD-L1 negative patients had 13.733 months, with no statistically significant difference (p=0.802). in the ICI group, PD-L1 positivity was numerically associated with longer survival, but this did not reach statistical significance (p=0.388) -. Patients with PD-L1 expression >50%(n:21) had an OS of 28.090 months, with no significant difference (p=0.966). Given the limited sample size and high proportion of missing PD-L1 data (77.4%), these findings should be considered exploratory and are presented in Supplementary Figure S1A–B.
3.2.4. Histological Subtype and OS
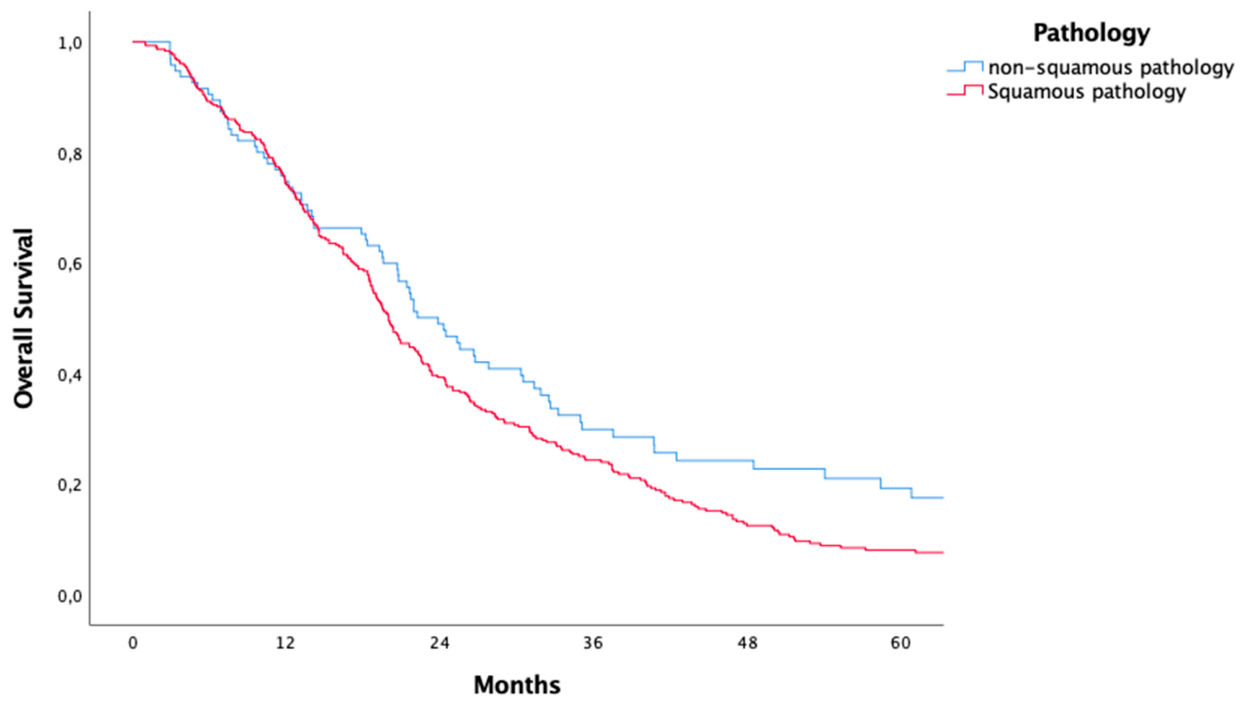
Patients with non-squamous histology had a median OS of 23.852 months, while those with squamous histology had 20.008 months (p=0.041) (Figure 3). However, this association lost independent significance in multivariate analysis
3.2.5. Effect of T and N Stage on OS
Neither T-stage (p=0.134) nor N-stage (p=0.693) was significantly associated with OS in univariate analysis (
Table 2
). This suggests that local stage at diagnosis may be less important than treatment-related factors (ICI use) and dynamic factors (progression timing) in determining post-progression outcomes.
3.3. Univariate and Multivariate Analyses
Univariate analysis (Table 2) identified post-progression ICI use (HR: 0.40, 95% CI: 0.29–0.55, p<0.001), early progression (HR: 2.84, 95% CI: 2.12–3.81, p<0.001), and non-squamous histology (HR: 0.74, 95% CI: 0.55–0.99, p=0.041) as significant prognostic factors.
Multivariate analysis (Table 3) confirmed post-progression ICI use as an independent prognostic factor (HR: 0.37, 95% CI: 0.25–0.54;p<0.001). Early progression was also identified as an independent negative prognostic factor(HR: 2.61, 95% CI: 1.91–3.57; p<0.001). PD-L1 status and histological subtype lost their independent significance in multivariate analysis.
Table 2.
Comparison of Overall Survival According to Post-Progression Treatment.
| Group | Median OS (months) | 95% CI | p-value* |
| Total patient population (n=403) | 26.743 | 18.892–34.594 | — |
| Post-progression ICI | <0.001 | ||
| ICI users (n=61) | 47.967 | 35.678–60.256 | |
| Non-ICI users (n=338) | 19.285 | 17.883–20.687 | |
| Early progression (≤6 months) | <0.001 | ||
| Yes (n=201) | 7.064 | 5.805–8.323 | |
| No (n=197) | 20.008 | 17.510–22.506 | |
| PD-L1 status (ICI group) | 0.388 | ||
| Positive (n=31) | 54.045 | 31.849–76.241 | |
| Negative (n=19) | 46.029 | 35.678–56.380 | |
| PD-L1 status (non-ICI group) | 0.802 | ||
| Positive (n=19) | 12.189 | 3.583–20.795 | |
| Negative (n=22) | 13.733 | 6.371–21.095 | |
| Histological subtype | 0.041 | ||
| Non-squamous (n=94) | 23.852 | 17.530–30.174 | |
| Squamous (n=305) | 20.008 | 17.883–22.133 | |
| T-stage | 0.134 | ||
| T1 (n=28) | 18.825 | 11.898–25.752 | |
| T2 (n=140) | 24.345 | 19.849–28.841 | |
| T3 (n=135) | 19.285 | 16.260–22.310 | |
| T4 (n=95) | 20.665 | 15.471–25.859 | |
| N-stage | 0.693 | ||
| N0 (n=48) | 19.515 | 13.242–25.788 | |
| N1 (n=43) | 20.797 | 14.154–27.440 | |
| N2 (n=248) | 20.797 | 17.964–23.630 | |
| N3 (n=58) | 18.366 | 11.456–25.276 |
*Log-rank test. OS: Overall survival; CI: Confidence interval; ICI: Immune checkpoint inhibitor.
Table 3.
Multivariate Cox Regression Analysis for Overall Survival.
| Variable | Comparison | HR | 95% CI | p-value |
| Post-progression ICI use | Yes vs. No | 0.37 | 0.25–0.54 | <0.001 |
| Early progression (≤6 months) | Yes vs. No | 2.61 | 1.91–3.57 | <0.001 |
| Histology | Non-squamous vs. Squamous | 0.82 | 0.60–1.12 | 0.208 |
| PD-L1 status | Positive vs. Negative | 0.91 | 0.65–1.27 | 0.578 |
| Stage III substage | IIIB vs. IIIA | 1.12 | 0.78–1.61 | 0.543 |
| IIIC vs. IIIA | 1.24 | 0.82–1.87 | 0.302 |
*HR: Hazard ratio; CI: Confidence interval; ICI: Immune checkpoint inhibitor. Statistically significant values (p<0.05) are shown in bold.
4. Discussion
This multicenter, large-cohort retrospective study is one of the most comprehensive evaluations to date of post-progression immunotherapy efficacy in patients with unresectable stage III NSCLC who did not receive durvalumab consolidation after definitive CRT. Our findings demonstrate that post-progression ICI was associated with a significant survival benefit (median OS 47.97 vs. 19.29 months), with early progression (≤6 months) emerging as the strongest negative prognostic factor. These results have important clinical implications for a patient population that is frequently encountered in routine oncology practice.
We defined overall survival (OS) from the date of documented disease progression to specifically evaluate the survival benefit associated with immunotherapy administered after progression. The time from CRT completion to progression was used solely to define early progression (≤6 months).
4.1. Comparison with the PACIFIC Trial and Other Studies
The median OS of 47.97 months observed in our post-progression ICI group is numerically comparable to the 47.5 months reported in the durvalumab consolidation arm of the PACIFIC trial [5,6]. However, direct comparison between these studies is not methodologically appropriate due to substantial differences in patient populations, eligibility criteria, treatment timing, and study design. Our cohort consisted of patients who, for various reasons, did not receive durvalumab consolidation—a group that is generally underrepresented in clinical trials. Nevertheless, the observation that these patients achieved similar survival outcomes with post-progression immunotherapy is clinically meaningful and suggests that later-line immunotherapy may partially compensate for the absence of consolidation durvalumab.
Prior to the PACIFIC era, studies such as CheckMate 153 and CheckMate 063 demonstrated median OS of 9–12 months with nivolumab in previously treated advanced NSCLC patients [12,13]. However, these studies predominantly included metastatic (stage IV) patients. Our findings extend this evidence to the stage III setting, specifically in patients without prior durvalumab exposure.
The Italian multicenter study by Crespi et al. reported favorable outcomes in patients receiving immunotherapy rechallenge after durvalumab progression [11]. Our study is the first large-cohort study to demonstrate the efficacy of post-progression immunotherapy in patients who did not receive durvalumab consolidation, addressing an important gap in the literature.
4.2. Early Progression as a Prognostic Factor
Early progression within 6 months after CRT emerged as the strongest negative prognostic factor in our study (HR: 2.61, p<0.001), with a median OS of only 7 months. This finding is consistent with the literature, where early progression after CRT is generally associated with primary refractory disease, aggressive tumor biology, or inadequate local control [14]. Importantly, only 31.1% of patients with early progression received post-progression ICI, likely due to rapid clinical deterioration. For these patients, more aggressive combination strategies (ICI + chemotherapy, ICI + anti-angiogenic agents) or referral to clinical trials may be more appropriate. Our results suggest that patients with early progression derive relatively less benefit from immunotherapy alone.
4.3. PD-L1 Expression and Immunotherapy Response
The role of PD-L1 expression in predicting immunotherapy response is well established in advanced NSCLC [15]. In our study, PD-L1-positive patients in the post-progression ICI group had a numerically longer median OS (54 months) compared to PD-L1-negative patients (46 months), though this did not reach statistical significance. This 8-month numerical difference is clinically noteworthy but should be interpreted with caution due to limited sample size (only 91 of 403 patients had documented PD-L1 status) and the high proportion of missing data (77.4%). The high rate of missing PD-L1 data reflects clinical practice in Turkiye during much of the study period, when PD-L1 testing was not routinely reimbursed.
Strikingly, in the non-ICI group, PD-L1-positive patients had shorter OS (12.19 months) than PD-L1-negative patients (13.73 months). This phenomenon—where PD-L1-high tumors may respond less favorably to conventional chemotherapy in the absence of immunotherapy—has been observed in other studies and underscores that avoiding immunotherapy in PD-L1-positive patients may be detrimental [16].
4.4. Histology, T-Stage, and N-Stage
Univariate analysis identified non-squamous histology as being associated with longer survival (23.85 vs. 20.01 months, p=0.041). However, this association lost independent significance in multivariate analysis (p=0.208), suggesting that the apparent prognostic advantage may be confounded by PD-L1 status or ICI use. The literature remains inconclusive regarding whether non-squamous histology confers greater benefit from immunotherapy [17].
Neither T-stage (p=0.134) nor N-stage (p=0.693) showed significant association with OS in our study. This unexpected finding may be explained by: (1) all patients received definitive CRT, which may have “standardized” the local stage; (2) systemic therapy (ICI use) may overshadow the prognostic impact of local stage; and (3) N2 disease was predominant in our cohort (61.5%), with a narrow distribution. These findings suggest that T and N stages should not be the sole determinants of post-progression treatment decisions; progression timing and PD-L1 status are more important dynamic factors.
4.5. Clinical Implications
Our results have several important clinical implications. First, in patients with stage III NSCLC who did not receive durvalumab consolidation, post-progression immunotherapy (nivolumab/pembrolizumab) represents a strong treatment option, associated with a significant improvement in OS. Second, patients with early progression (within 6 months after CRT) have a very poor prognosis and may require more aggressive combination regimens or clinical trial enrollment; immunotherapy alone may not be sufficient. Third, PD-L1-positive patients have a very poor prognosis with conventional chemotherapy if they do not receive immunotherapy (only 12 months in this cohort). Therefore, post-progression immunotherapy should be strongly considered in patients with PD-L1 positivity (especially >1%). Finally, T and N stage should not be the sole determinants of post-progression treatment decisions; progression timing and PD-L1 status are more important factors.
4.6. Strengths and Limitations
Our study has several notable strengths: large sample size (n=403) —one of the largest cohorts in this patient population; multicenter design, enhancing generalizability; being one of the first studies to focus specifically on patients who did not receive durvalumab consolidation, addressing a common clinical scenario; and clear definition of early progression (within 6 months) with demonstration of its prognostic value.
However, several limitations must be acknowledged. First, the retrospective design introduces inherent selection and recall biases. Although we attempted to adjust for this using multivariate Cox regression, residual confounding may persist. Second, ECOG performance status was documented as 0–1 for all included patients; however, detailed ECOG data at the time of progression were not available for all patients. Third, PD-L1 status was available for only 22.6% of patients, which is a common limitation of retrospective studies and limits the power of our PD-L1-related analyses. Fourth, the heterogeneity of treatment protocols—the agents used in the ICI group (nivolumab and pembrolizumab) and treatment durations were not standardized, and treatments in the non-ICI group (platinum-based chemotherapy, docetaxel, best supportive care, etc.) were also heterogeneous. Fifth, the small sample size in subgroup analyses (e.g., PD-L1 positive/negative) limits statistical power. Sixth, median follow-up time was 28.4 months (IQR: 18.2–41.6 months). Seventh, our findings are hypothesis-generating and require prospective validation. Despite these limitations, our findings are supported by robust statistical analyses and address an important gap in the literature.
5. Conclusions
This multicenter retrospective study demonstrates that post-progression immunotherapy was associated with a significant survival benefit in patients with stage III NSCLC who did not receive durvalumab consolidation, with a median OS approaching 48 months. Early progression (within 6 months after CRT) was identified as the strongest negative prognostic factor. PD-L1 positivity was numerically associated with longer survival, particularly in patients receiving immunotherapy, though this finding should be considered exploratory due to the high rate of missing PD-L1 data. These findings suggest that immunotherapy should be considered in patients who progress after CRT without prior durvalumab consolidation, provided performance status is adequate. This patient population is frequently encountered in oncological practice and currently lacks a standard approach; our study provides important evidence to guide clinical decision-making. Prospective studies are needed to confirm these findings and to identify optimal patient selection strategies.
Supplementary Materials
The following supporting information can be downloaded at the website of this paper posted on Preprints.org. Supplementary Figure S1A–B: Kaplan-Meier curves for overall survival in PD-L1 negative and PD-L1 positive patients according to post-progression immunotherapy use.
Author Contributions
Conceptualization, [B.B] and [S.Y]; methodology, [B.B] and [S.Y]; software, [S.Y]; validation, [B.B], [S.Y] and [O.Ö.E]; formal analysis, [S.Y]; investigation, [B.B] and [S.Y]; resources, [B.B, O.Ö.E, B.U, C.C, İ.T.Y, M.E, S.Y, H.B, B.E.K, M.A, H.A, A.P.E]; data curation, [B.B, B.E.K, H.A, H.B, B.U]; writing—original draft preparation, [B.B]; writing—review and editing, [B.B, O.Ö.E, B.U, C.C, İ.T.Y, M.E, S.Y, H.B, B.E.K, M.A, H.A, A.P.E]; visualization, [B.B]; supervision, [S.Y]; project administration, [B.B]; funding acquisition, Not applicable. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board (or Ethics Committee) of Selçuk University, protocole code:E-70632468-050.01-1181902 and date of approval 27.01.2026
Informed Consent Statement
Patient consent was waived due to the retrospective nature of the study, which involved no direct patient contact or intervention, and all data were analyzed anonymously.
Data Availability Statement
The data supporting the findings of this study are available from the corresponding author upon reasonable request. Due to ethical restrictions and patient privacy, the data are not publicly available. De-identified data will be shared with researchers who provide a methodologically sound proposal, subject to approval by the institutional ethics committee and a signed data access agreement.
Acknowledgments
The authors would like to thank all participating centers and their staff for their contributions to patient data collection. During the preparation of this manuscript, the authors used ChatGPT (OpenAI, GPT-4) for language editing and grammatical refinement purposes only. The authors have reviewed and edited the output and take full responsibility for the content of this publication.
Conflicts of Interest
The authors declare no conflicts of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Abbreviations
| Abbreviation | Definition |
| NSCLC | Non-small cell lung cancer |
| CRT | Chemoradiotherapy |
| ICI | Immune checkpoint inhibitor |
| OS | Overall survival |
| HR | Hazard ratio |
| CI | Confidence interval |
| PS | Performance status |
| PD-L1 | Programmed death-ligand 1 |
| RECIST | Response Evaluation Criteria in Solid Tumors |
| SPSS | Statistical Package for the Social Sciences |
References
- Sung, H.; Ferlay, J.; Siegel, R.L.; et al. Global Cancer Statistics 2020: GLOBOCAN Estimates of Incidence and Mortality Worldwide for 36 Cancers in 185 Countries. CA Cancer J. Clin. 2021, 71(3), 209–249. [Google Scholar] [CrossRef] [PubMed]
- Provencio, M.; Carcereny, E.; Rodriguez-Abreu, D.; et al. Real-World Outcomes of Chemoradiotherapy in Patients with Stage II/III Non-Small-Cell Lung Cancer in the Durvalumab Era: An Observational Study. 2025. [Google Scholar] [CrossRef] [PubMed]
- Antonia, S.J.; Villegas, A.; Daniel, D.; et al. Durvalumab after Chemoradiotherapy in Stage III Non-Small-Cell Lung Cancer. N Engl. J. Med. 2017, 377(20), 1919–1929. [Google Scholar] [CrossRef] [PubMed]
- Bradley, J.D.; Paulus, R.; Komaki, R.; et al. Long-term survival of patients with stage III non-small cell lung cancer (NSCLC) treated with chemoradiotherapy: A secondary analysis of RTOG 9410. Int. J. Radiat. Oncol. Biol. Phys. 2015, 93(3), E383. [Google Scholar]
- Antonia, S.J.; Villegas, A.; Daniel, D.; et al. Overall Survival with Durvalumab after Chemoradiotherapy in Stage III NSCLC. N Engl. J. Med. 2018, 379(24), 2342–2350. [Google Scholar] [CrossRef] [PubMed]
- Spigel, D.R.; Faivre-Finn, C.; Gray, J.E.; et al. Five-Year Survival Outcomes With Durvalumab After Chemoradiotherapy in Unresectable Stage III NSCLC: An Update From the PACIFIC Trial. J. Thorac. Oncol. 2021, 16(3), S16–S17. [Google Scholar]
- Markman, B.; et al. Durvalumab consolidation after chemoradiotherapy in unresectable stage III non-small cell lung cancer: A real-world experience from the Australian subset of PACIFIC-R. Cancer Treat. Res. Commun. 2025. [Google Scholar] [CrossRef] [PubMed]
- LACOG 0120 Study Group. Durvalumab as consolidation therapy in patients who received chemoradiotherapy for unresectable stage III NSCLC: Real-world data from an expanded access program in Brazil. J. Bras. Pneumol. 2024, 50(6), e20240228. [Google Scholar] [CrossRef] [PubMed]
- Real-world outcomes of subsequent treatment strategies after durvalumab consolidation in stage III unresectable non-small cell lung cancer. Lung Cancer 2025, 204, 108576. [CrossRef] [PubMed]
- Kareff, S.A.; Han, S.; Haaland, B.; et al. International cost-effectiveness analysis of durvalumab in stage III non-small cell lung cancer. JAMA Netw. Open 2024, 7(5), e2413938. [Google Scholar] [CrossRef] [PubMed]
- Crespi, V.; Delcuratolo, M.D.; Minuti, G.; et al. Real-world outcomes of subsequent treatment strategies after durvalumab consolidation in stage III unresectable non-small cell lung cancer. Lung Cancer 2025, 204, 108576. [Google Scholar] [CrossRef] [PubMed]
- Borghaei, H.; et al. Nivolumab versus Docetaxel in Advanced Nonsquamous Non-Small-Cell Lung Cancer. N Engl. J. Med. 2015, 373(17), 1627–1639. [Google Scholar] [CrossRef] [PubMed]
- Rizvi, N.A.; et al. Nivolumab in Previously Treated Non-Small-Cell Lung Cancer. J. Clin. Oncol. 2015, 33(18), 2004–2012. [Google Scholar] [CrossRef] [PubMed]
- Ahn, J.S.; et al. Early progression after chemoradiotherapy in stage III NSCLC. Lung Cancer 2019, 136, 45–51. [Google Scholar]
- Reck, M.; et al. Pembrolizumab versus Chemotherapy for PD-L1-Positive Non-Small-Cell Lung Cancer. N Engl. J. Med. 2016, 375(19), 1823–1833. [Google Scholar] [CrossRef] [PubMed]
- Mok, T.S.K.; Wu, Y.L.; Kudaba, I.; et al. Pembrolizumab versus chemotherapy for previously untreated, PD-L1-expressing, locally advanced or metastatic non-small-cell lung cancer (KEYNOTE-042): a randomised, open-label, controlled, phase 3 trial. Lancet 2019, 393(10183), 1819–1830. [Google Scholar] [CrossRef] [PubMed]
- Gainor, J.F.; et al. Histology and immunotherapy in NSCLC. J. Thorac. Oncol. 2019, 14(8), 1365–1375. [Google Scholar] [CrossRef]
- Zhou, F.; et al. PD-L1 expression and ICI efficacy in stage III NSCLC. Eur. J. Cancer 2024, 208, 114187. [Google Scholar]
- NSCLC Meta-Analyses Collaborative Group. Chemoradiotherapy vs radiotherapy in stage III NSCLC. J. Clin. Oncol. 2023, 41(25), 4089–4101.
- Garassino, M.C.; et al. Immunotherapy in NSCLC: histology matters. J. Thorac. Oncol. 2024, 19(6), 892–904. [Google Scholar]
- Hellmann, M.D.; et al. Nivolumab plus Ipilimumab in Advanced Non-Small-Cell Lung Cancer. N Engl. J. Med. 2019, 381(21), 2020–2031. [Google Scholar] [CrossRef] [PubMed]
- Felip, E.; et al. Adjuvant atezolizumab after adjuvant chemotherapy in resected stage IB-IIIA non-small-cell lung cancer (IMpower010): a randomised, multicentre, open-label, phase 3 trial. Lancet Oncol. 2021, 22(8), 1076–1089. [Google Scholar]
- Chaft, J.E.; et al. Evolution of systemic therapy for stage III non-small cell lung cancer. Nat. Rev. Clin. Oncol. 2025, 22(1), 23–38. [Google Scholar]
- Peters, S.; et al. Durvalumab in stage III NSCLC: five-year outcomes from the PACIFIC trial. J. Clin. Oncol. 2022, 40((16_) suppl, 8512. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Kaplan-Meier curves for overall survival (OS) according to post-progression immunotherapy (ICI) use. Patients who received ICI after progression (n=61) had significantly longer median OS compared to those who did not receive ICI (n=338) (47.967 months [95% CI: 35.678–60.256] vs. 19.285 months [95% CI: 17.883–20.687]; log-rank p<0.001). Censored patients are indicated by tick marks on the curves. ICI: immune checkpoint inhibitor; OS: overall survival; CI: confidence interval.
Figure 1.
Kaplan-Meier curves for overall survival (OS) according to post-progression immunotherapy (ICI) use. Patients who received ICI after progression (n=61) had significantly longer median OS compared to those who did not receive ICI (n=338) (47.967 months [95% CI: 35.678–60.256] vs. 19.285 months [95% CI: 17.883–20.687]; log-rank p<0.001). Censored patients are indicated by tick marks on the curves. ICI: immune checkpoint inhibitor; OS: overall survival; CI: confidence interval.
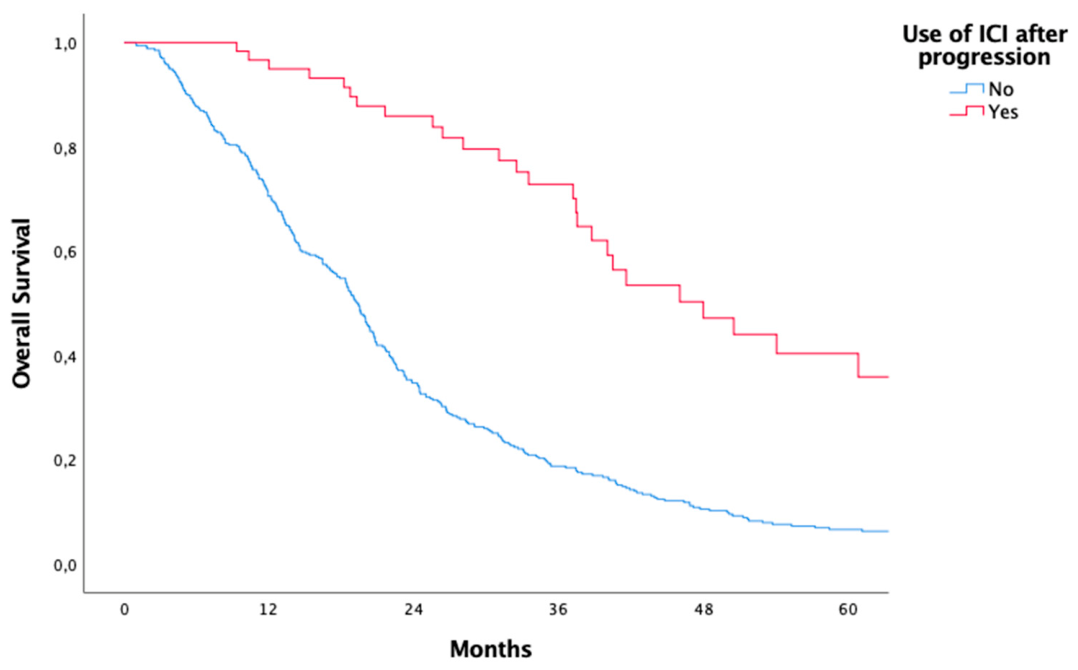
Figure 2.
Kaplan-Meier curves for overall survival (OS) according to timing of progression after chemoradiotherapy (CRT). Patients who progressed within the first 6 months after CRT (early progression, n=201) had a significantly shorter median OS compared to those who progressed after 6 months (late progression, n=197): 7.064 months (95% CI: 5.805–8.323) vs. 20.008 months (95% CI: 17.510–22.506); log-rank p<0.001. Censored patients are indicated by tick marks on the curves. Early progression was identified as a strong negative prognostic factor. OS: overall survival; CI: confidence interval; CRT: chemoradiotherapy.
Figure 2.
Kaplan-Meier curves for overall survival (OS) according to timing of progression after chemoradiotherapy (CRT). Patients who progressed within the first 6 months after CRT (early progression, n=201) had a significantly shorter median OS compared to those who progressed after 6 months (late progression, n=197): 7.064 months (95% CI: 5.805–8.323) vs. 20.008 months (95% CI: 17.510–22.506); log-rank p<0.001. Censored patients are indicated by tick marks on the curves. Early progression was identified as a strong negative prognostic factor. OS: overall survival; CI: confidence interval; CRT: chemoradiotherapy.
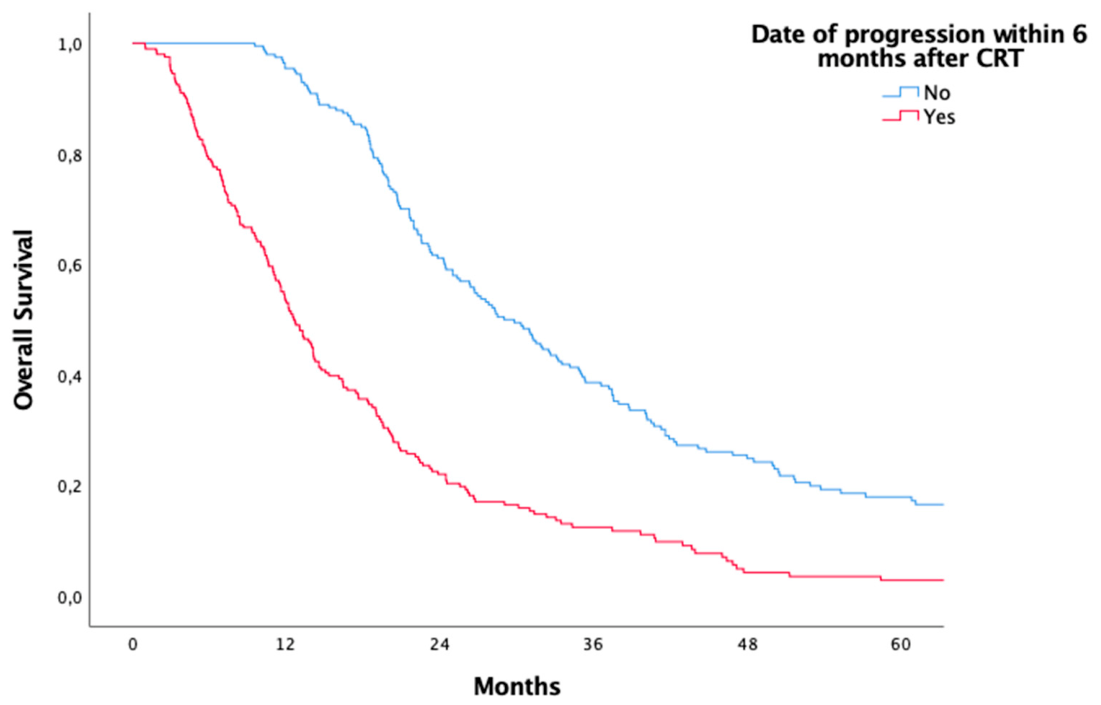
Figure 3.
Kaplan-Meier curves for overall survival (OS) according to histological subtype. Patients with non-squamous histology (n=94) had a significantly longer median OS compared to those with squamous histology (n=305) (23.852 months [95% CI: 17.530–30.174] vs. 20.008 months [95% CI: 17.883–22.133]; log-rank p=0.041). Censored patients are indicated by tick marks on the curves. OS: overall survival; CI: confidence interval.
Figure 3.
Kaplan-Meier curves for overall survival (OS) according to histological subtype. Patients with non-squamous histology (n=94) had a significantly longer median OS compared to those with squamous histology (n=305) (23.852 months [95% CI: 17.530–30.174] vs. 20.008 months [95% CI: 17.883–22.133]; log-rank p=0.041). Censored patients are indicated by tick marks on the curves. OS: overall survival; CI: confidence interval.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.