

Submitted:
03 July 2026
Posted:
06 July 2026
You are already at the latest version
Abstract
Objectives: To assess the impact of magnetic resonance imaging (MRI) versus computed tomography (CT) on target delineation and dosimetry in adjuvant vaginal cuff brachy-therapy (VBT) for endometrial cancer.
Methods: Twenty-five consecutive patients receiving adjuvant high-dose-rate VBT after hysterectomy were prospectively included. All underwent standardized treatment using a vaginal cylinder with a fixed loading pattern; individualized optimization was permitted for suboptimal coverage or proximity of organs at risk (OARs). For each patient, clinical target volume (CTV) and OARs (bladder, rectum, sigmoid, bowel) were contoured on both CT and MRI. Dosimetric parameters (CTV D90, D98, D50; OAR D2cc) were compared. Treatment characteristics and outcomes were analyzed retrospectively.
Results: Median CTV was smaller on MRI (9.8 cm³) than on CT (13.6 cm³). CTV coverage was comparable between modalities, with mean EQD2 D90 of 5.32 Gy per fraction on MRI versus 5.10 Gy per fraction on CT (p=0.433), and mean EQD2 D98 of 3.95 Gy per fraction on MRI versus 3.80 Gy per fraction on CT (p=0.491). In contrast, EQD2 D50 was signifi-cantly higher on MRI-based plans than on CT-based plans (9.12 vs 8.62 Gy per fraction, p=0.012). OAR D2cc values showed no significant differences between modalities. Most patients (80%) were treated with the institutional standard plan (5 Gy at 5 mm depth), and 20% required individualized optimization. After a median follow-up of 25 months (range 0–72), five patients (20%) recurred (one local, one regional, three distant), and one (4%) died. No grade ≥3 gastrointestinal or genitourinary toxicities occurred.
Conclusions: MRI-based planning delineated smaller CTVs but yielded no clinically rele-vant dosimetric advantage. CT-based planning remains sufficient for safe and effective adjuvant VBT, whereas MRI may be reserved for complex or investigational cases.
Keywords:
endometrial cancer
; vaginal cuff brachytherapy
; MRI
; CT
1. Introduction
Endometrial cancer is the most common female pelvic malignancy in developed countries, with an incidence of about 140,000 per year or 15.5 per 100,000 women in Europe according to GLOBOCAN 2022 [1]. Standard primary treatment of localized tumors consists of total hysterectomy with bilateral salpingo-oophorectomy, with or without lymph node staging, followed by adjuvant radiotherapy in selected patients based on risk factors [2]. Postoperative brachytherapy has been shown to significantly reduce local recurrence rates. The PORTEC-2 trial demonstrated that vaginal brachytherapy (VBT) alone decreased the 15-year vaginal recurrence rate from 15% to 5% in patients with high-intermediate risk disease [3].
Traditionally, intracavitary VBT was planned using two-dimensional X-ray imaging after insertion of a vaginal cylinder and a rectal probe for in vivo dosimetry. The standard approach involved prescribing dose at 5 mm depth, assuming a uniform vaginal wall thickness of 5 mm. This method, still used in recent multicenter trials [4], has several limitations in terms of anatomical accuracy and dose conformity.
With the advent of modern cross-sectional imaging, computed tomography has largely replaced X-ray-based planning, allowing for improved visualization of applicator placement and adjacent organs at risk. However, CT’s limited soft tissue contrast remains a drawback. Evidence from cervical cancer brachytherapy shows that CT-based target volumes tend to overestimate tumor extent compared to MRI, potentially resulting in unnecessary irradiation of organs at risk (OARs) [5].
Previous studies have investigated the influence of different cylinder sizes [6], angles [7], applicator types [8], and treatment durations [9] on dose distribution. Yet, the specific dosimetric differences between CT- and MRI-based planning have mostly been explored in phantom models [10] or in the setting of primary radiotherapy with an intact uterus [11,12]. Importantly, a retrospective MRI-based evaluation of previously CT-planned VBT demonstrated underdosage of the clinical target volume (CTV) in over half of patients [13].
Given MRI’s superior soft tissue contrast, it may offer significant advantages for precise target delineation and optimized sparing of OARs in adjuvant VBT. Despite its increasing use in gynecologic brachytherapy, particularly for cervical cancer, MRI guidance has not yet become standard for endometrial cancer.
The integration of MRI into adjuvant brachytherapy planning could potentially improve treatment accuracy, reduce toxicities, and pave the way for dose escalation or adaptive strategies in selected patients. However, data on its implementation, benefits, and clinical impact remain limited.
The aim of this study is to evaluate the potential role of MRI-guided planning in adjuvant vaginal cuff brachytherapy for endometrial cancer. Specifically, we compare MRI with CT-based planning in terms of target volume, coverage and OAR dose exposure, as well as clinical outcome.
2. Materials and Methods
Patients and Treatment
This is a prospective single-center cohort study which was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Ethics Committee of Medical University of Vienna (protocol code 1397/2018). Informed consent was obtained from all patients involved in the study. Between 2018 and 2021, patients with histologically confirmed endometrial carcinoma were included after undergoing total hysterectomy with bilateral salpingo-oophorectomy with or without lymph node sampling. Adjuvant therapy consisted of VBT alone or in combination with external beam radiotherapy or chemotherapy.
A vaginal cylinder applicator commercialized by Elekta AB with diameters between 25 and 40 mm was used (Figure 1). Applicator size was selected individually after clinical examination and measurement of vaginal length to ensure optimal fit and mucosal contact.
Patients were positioned in lithotomy, and a Foley catheter was placed at the first fraction to allow bladder filling control. The cylinder was assembled and inserted under direct visualization. At the first fraction, imaging was performed to support treatment planning: orthogonal X-rays for applicator position verification (performed at every fraction as part of standard practice), and in addition, CT and MRI were acquired in close temporal proximity with the applicator in situ for this study. The clinical workflow is exemplified in Figure 2.
The institutional standard consisted of prescribing 5 Gy at 5 mm tissue depth in the proximal third of the vagina, delivered in 4 fractions of 5 Gy each fort the exclusive brachytherapy treatment. The following parameters were collected: age, histology, TNM stage, grading, margin status, lymphovascular invasion, use of chemotherapy or external beam radiotherapy, number of fractions of VBT, cylinder size, recurrences and side effects.
The objective of this study is to compare CT-based and MRI-based planning in adjuvant vaginal cuff brachytherapy by analyzing CTV and dose parameters for both target and OARs. Specifically, we aim to:
- Quantify differences in CTV volume delineated on CT versus MRI
- Evaluate D90 and other dose parameters for the CTV on each modality
- Compare dose exposure to OARs (bladder, rectum, sigmoid colon)
- Evaluate in how many patients imaging-based planning (CT or MRI) would have led to modifications of the standard X-ray–based prescription (5 Gy at 5 mm)
- Report treatment outcomes and patients‘ demographics in this cohort
Imaging
X-ray - Orthogonal X-ray images were obtained in anteroposterior and lateral planes with the vaginal cylinder in place to verify applicator geometry and anatomical position.
CT - CT imaging was performed using a Somatom Definition AS Siemens with a slice thickness of 2 mm. Patients were positioned in a supine position, without intravenous or oral contrast. CT images were used for contouring the CTV and OARs on axial images and for generating CT-based treatment plans.
MRI - MRI was performed using an open, low field Magnetom C system (Siemens) according to the Groupe Européen de Curiethérapie – European Society for Radiotherapy and Oncology (GEC-ESTRO) recommendations for image-guided brachytherapy. T2-weighted sequences were acquired in axial, para-axial, coronal, and sagittal planes covering the vaginal cuff and adjacent pelvic organs with the applicator in place. Slice thickness was 5 mm. MRI images were used for CTV and OAR delineation and for generation of MRI-based treatment plans.
Contouring and Planning
On both CT and MRI, the CTV, bladder, rectum, sigmoid, small bowel, and urethra were contoured by a radiation oncologist with at least 3 years of experience in brachytherapy. Contouring was performed independently on CT and MRI (Figure 3).
For each patient, three plans were generated:
- X-ray–based standard plan (5 Gy at 5 mm tissue depth in the proximal third of the vagina - determined during clinical examination prior to the first application by measuring the vaginal length)
- CT-based plan,
- MRI-based plan
Plans were created in Oncentra Treatment Planning System, version 4.6.1, using Points-Distance Optimisation, Geometrical-Distance Optimisation or manual optimisation. Dose–volume histogram (DVH) parameters were calculated for the CTV (D90, D98, V100) and OARs (D2cc for bladder, rectum, sigmoid, small bowel). Absorbed dose was reported in Gy and converted to biologically equi-effetive dose in 2 Gy fractions (EQD2), (α/β = 10 Gy for CTV, 3 Gy for OARs).
Plan Adaptation
For each patient, we assessed whether imaging-based planning (CT or MRI) would have led to a modification of the institutional X-ray–based standard plan (5 Gy prescribed at 5 mm tissue depth over the proximal third of the vagina). Any deviations from the standard plan were documented, including adjustments in prescription depth (e.g., increased to 7 mm to ensure adequate target coverage in cases with a thicker vaginal wall, or reduced to 3 mm to limit dose to adjacent bowel loops), modifications of the treated length, or changes in channel activation patterns and dwell time optimization. These adaptations were used to classify each case as either treated with the standard plan or requiring individualized, image-guided optimization.
Statistical Analysis
Descriptive statistics were reported as median, mean ± standard deviation, and interquartile ranges. Normality was tested with the Shapiro–Wilk test. Comparisons between CT- and MRI-based plans were performed using paired t-tests. A two-sided p-value < 0.05 was considered statistically significant. Analyses were carried out using SPSS statistics (version 24, IBM, Armonk, NY, USA).
During the preparation of this work the authors used ChatGPT to improve readability and language. After using this tool, the authors reviewed and edited the content as needed and take full responsibility for the content of the publication.
3. Results
3.1. Patient Characteristics
A total of 25 consecutive patients were included in the study. Patient and treatment characteristics are presented in Table 1.
The median age at diagnosis was 65 years (range: 51–80 years).
Most patients presented with early-stage disease: T1a (n=7, 28%), T1b (n=9, 36%), and T2 (n=7, 28%), while two patients (8%) had T3a disease. Nodal status was predominantly negative (N0, n=23, 92%), with 1 patient N1 (4%) and 1 patient Nx (4%).
Lymph node assessment was performed in nearly all cases: 12 patients (48%) underwent sentinel lymph node biopsy (SNL) followed by lymphadenectomy, 11 patients (44%) SNL, and 2 patients (8%) had only imaging nodal evaluation.
Histology was mainly endometrioid adenocarcinoma (n=16, 63%), followed by serous/papillary carcinoma (n=3, 12%), mixed histology (n=2, 8%), carcinosarcoma (n=3, 12%), and clear cell carcinoma (n=1, 4%). Tumor grading showed low grade in 8 patients (32%), high grade in 13 (52%), and unknown in 4 patients (16%). Molecular pathology analysis has not been standard at the time of the trial execution and has therefore not been performed in the included patients at diagnosis.
Significant lymphovascular invasion was present in 2 patients (8%) (L1), while vascular invasion was documented in 1 patient (4%). Resection margins were negative (R0) in 20 patients (80%); in 5 cases, margin status was not explicitly reported.
3.2. Clinical Outcomes
With a median follow-up of 25 months (range 0–72 months), 5 patients (20%) developed recurrences: one local, one regional, and three distant. At the time of analysis, 24 patients (96%) were alive, while 1 patient (4%) had died of metastatic disease.
Treatment was well tolerated. No grade ≥3 genitourinary or gastrointestinal toxicities were reported.
In our series, only one patient developed a local recurrence after guideline-concordant adjuvant therapy. She had a stage pT2N0 (FIGO II) grade 2 endometrioid adenocarcinoma with extensive lymphovascular invasion, treated with surgery, six cycles of adjuvant carboplatin/paclitaxel, and vaginal brachytherapy (20 Gy in 4 fractions prescribed at 5 mm depth) in March 2020. A first recurrence occurred in May 2021, presenting as multifocal disease in the lower vaginal third. Salvage therapy with EBRT and PDR brachytherapy was delivered to 74 Gy. Histology at that time showed ER/PR-positive endometrioid adenocarcinoma, p53 wildtype, and p16 patchy; MMR status was not assessed.
In July 2024, she experienced a second recurrence, involving the right pelvic sidewall with ureteral obstruction and a contralateral vaginal focus. Biopsy confirmed recurrent endometrioid adenocarcinoma, MMR-deficient, p53 wildtype, ER/PR positive, and HER2 negative. Immunotherapy with dostarlimab was initiated and remains ongoing.
3.3. Treatment Characteristics
All 25 patients completed adjuvant vaginal cuff brachytherapy as prescribed. All patients received 4 fractions. Vaginal cylinder diameter ranged from 25 to 40 mm. The most frequently used applicator size was 30 mm (48%), followed by 35 mm (36%), 25 mm (12%), and 40 mm (4%).
3.3.1. Target Volume and Dosimetric Analysis
The median CTV volume was 9.8 cm³ (range: 4.5–31.2) on MRI compared to 13.6 cm³ (range: 5.9–28.0) on CT. The mean CTV volume was 10.9 cm³ on MRI vs 13.9 cm³ on CT, corresponding to an average relative reduction of approximately 21% with MRI-based delineation (Table 2).
This difference was statistically significant (paired t-test, p = 0.00035).
Dose coverage of the CTV on MRI- and CT is summarised in Table 2. The mean EQD2 D90 was 5.32 Gy per fraction for MRI vs 5.10 Gy per fraction for CT (p = 0.433), and the mean EQD2 D98 was 3.95 Gy per fraction for MRI vs 3.80 Gy per fraction for CT (p = 0.491), with no significant differences. In contrast, the EQD2 D50 was significantly higher on MRI-based plans (9.12 Gy vs 8.62 Gy per fraction, p = 0.012).
3.3.2. Organs at Risk Dosimetry
The volume and the dose exposure to organs at risk (D2cm³, EQD2) was similar between CT- and MRI-based planning (Table 3).
For the bladder, the mean D2cm³ in EQD2 was 7.6 Gy per fraction on MRI and 7.4 Gy per fraction on CT, with a mean difference of +0.2 Gy. The difference was not statistically significant (p = 0.44).
For the rectum, mean D2cm³ in EQD2 was 6.3 Gy per fraction on MRI compared to 6.3 Gy per fraction on CT, with a negligible difference of +0.0 Gy (p = 0.87).
For the sigmoid, mean D2cm³ in EQD2 was 3.2 Gy per fraction on MRI and 3.2 Gy per fraction on CT, with a mean difference of +0.0 Gy (p = 0.97).
For the bowel, mean D2cm³ in EQD2 was 4.0 Gy per fraction on MRI versus 3.9 Gy per fraction on CT, with a difference of +0.1 Gy (p = 0.81).
For the urethra, mean D2cm³ in EQD2 was 2.3 Gy per fraction on MRI compared to 2.5 Gy per fraction on CT, with a difference of –0.2 Gy. This trend towards lower urethral dose on MRI was not statistically significant (p = 0.11).
3.3.3. Treatment Plan Adaptations
Of the 25 patients, 20 (80%) were treated with the institutional standard plan (prescription 5 Gy at 5 mm tissue depth), while 5 (20%) required an individualized plan, all of which were manually optimized in order to cover the asymmetrical edges of the vaginal cuff.
4. Discussion
In this prospective single-institution analysis of 25 patients undergoing adjuvant vaginal cuff brachytherapy for endometrial cancer, we directly compared CT- and MRI-based planning. Our results demonstrate that MRI systematically delineated smaller CTV volumes than CT, yet target coverage (D90, D98) was preserved, and only D50 differed significantly, being higher on MRI-based plans. OAR doses (D2cc for bladder, rectum, sigmoid, bowel, and urethra) were comparable between modalities.
From a planning perspective, most patients (80%) were treated according to the institutional standard plan, consisting of 5 Gy prescribed at 5 mm tissue depth in the proximal third of the vagina. In 5 patients (20%), individualized plans were required, reflecting the added value of image-based workflows for selected cases. Adaptations were mainly performed to account for patient-specific anatomy. These individualized adjustments highlight the potential of cross-sectional imaging to guide more personalized planning beyond a uniform depth prescription.
Clinically, treatment was well tolerated, with no grade ≥3 toxicities and a low recurrence rate over a median follow-up of 25 months. Only one patient experienced a local vaginal recurrence, while three developed distant metastases.
Together, these findings indicate that MRI-based planning is feasible and modifies target delineation compared to CT, resulting in smaller but adequately covered volumes without increasing OAR doses. Although MRI delineated systematically smaller CTV volumes than CT, this difference did not translate into clinically meaningful dosimetric advantages. Target coverage remained comparable between the two modalities (D90 and D98), and OAR doses were essentially unchanged. The only statistically significant difference observed was a modest increase in D50 on MRI-based plans, which is unlikely to have clinical relevance.
These results suggest that, unlike in cervical cancer where MRI has become indispensable for brachytherapy planning, the added value of MRI in postoperative vaginal cuff brachytherapy appears limited. In this context, CT provides sufficient anatomical definition to achieve adequate target coverage and safe OAR constraints, especially when planning is guided by institutional standards and clinical experience
The role of MRI in postoperative VBT planning has been explored only in a few studies, and evidence remains limited. Chapman et al. reported frequent underdosage of the vaginal cuff when evaluated retrospectively on MRI after standard cylinder brachytherapy, with up to half of patients having at least 1 cm³ of target volume receiving less than 50% of the prescribed dose [13]. They hypothesized that such undercoverage could contribute to local failures. In contrast, our analysis did not confirm systematic underdosage when comparing CT- and MRI-based plans; CTV coverage (D90/D98) was preserved on both modalities. This suggests that in routine practice, the conventional prescription depth of 5 mm remains adequate for most patients.
Other feasibility studies have supported the technical implementation of MRI-guided cylinder brachytherapy. Owrangi et al. demonstrated that MRI-based planning was feasible and reproducible, providing high-quality images for contouring and dose optimization [10]. Gebhardt et al. and Jordan et al. further reported encouraging clinical outcomes with MRI-guided image-based brachytherapy in patients with inoperable endometrial cancer [11,12]. However, these studies focused on primary or definitive settings rather than the adjuvant context.
Our results differ in that they directly compare CT and MRI in the postoperative adjuvant setting, showing no dosimetric advantage of MRI over CT. This finding suggests that while MRI may improve anatomical delineation, its clinical impact is less pronounced in VBT compared with definitive treatment of endometrial or cervical cancer, where target definition and OAR proximity are far more complex.
The role of adjuvant VBT in endometrial cancer has undergone significant changes in recent years. Traditionally, VBT was a widely applied standard in the postoperative management of intermediate- and high-intermediate–risk EC, supported by trials such as PORTEC-2, which demonstrated excellent local control with reduced toxicity compared to EBRT [3]. However, the advent of molecular pathology and the results of PORTEC-4a are shifting treatment algorithms toward a more individualized risk stratification [14]. Integration of The Cancer Genome Atlas (TCGA)–based molecular classification enables more refined patient selection, and many low-risk subgroups are now considered for observation alone, reducing the number of patients receiving adjuvant VBT. Therefore, the current and future role of VBT is becoming more selective, focusing on those patients who are at genuine risk of local relapse despite otherwise favorable features [15].
In this context, the optimization of VBT planning becomes even more relevant. If fewer patients are offered adjuvant brachytherapy, the subset that remains eligible is enriched with those at higher risk of relapse and those who may most benefit from precise treatment.
Despite excellent local control rates with adjuvant vaginal brachytherapy, isolated local recurrences may still occur, particularly in patients with unfavorable biological features. In our cohort, one patient developed a local recurrence despite guideline-concordant adjuvant therapy, providing valuable insight into potential biological and dosimetric factors underlying such events.
This patient was subsequently found to have an MMR-deficient molecular subtype, which is associated with an increased risk of locoregional recurrence [15] despite adequate local treatment. This molecular profile, identified only at the time of the second recurrence, likely contributed to the unfavorable disease course.
The multifocal vaginal relapse also raises dosimetric considerations. Standard prescriptions of 5 Gy at 5 mm depth may not always achieve adequate coverage of the vaginal cuff, particularly in patients with thicker vaginal walls or atypical anatomy. Chapman et al. demonstrated that conventional prescription depth frequently results in underdosage at the vaginal apex on MRI, which may contribute to local failure in selected cases [13]. While our dosimetric analysis did not reveal systematic undercoverage, this case illustrates how aggressive tumor biology and subtle dosimetric uncertainties can converge to produce local recurrence in a minority of patients.
These observations support a more individualized approach to adjuvant treatment, integrating molecular classification with optimized image-guided planning. MRI-based planning could allow tailored prescription depths or coverage in anatomically complex cases, while molecular profiling can identify patients who may benefit from intensified or combined adjuvant strategies beyond standard VBT.
Strengths and Limitations
The main strengths of this study are its prospective imaging-based design with systematic comparison of CT- and MRI-based planning in a homogeneous cohort of consecutive postoperative EC patients, and the detailed dosimetric analysis of both target coverage and organ-at-risk doses. Furthermore, clinical outcomes with a median follow-up of more than two years were available, adding translational relevance.
However, several limitations must be acknowledged. First, the study sample size was relatively small, limiting the power to detect subtle dosimetric or clinical differences. Second, treatment planning was based on single-fraction imaging, without repeated MRI during subsequent fractions, which may not account for intra-patient anatomical variations.
5. Conclusions
In this prospective comparison of CT- and MRI-based planning for adjuvant vaginal cuff brachytherapy in endometrial cancer, MRI delineation resulted in slightly smaller CTV volumes and a higher D50, but no significant differences in clinically relevant coverage parameters or organ-at-risk doses. These findings suggest that while MRI provides superior soft-tissue visualization, its added value for standard adjuvant VBT appears limited in routine practice.
With the ongoing shift toward molecular risk stratification and decreasing indications for VBT, the role of advanced imaging in this setting may become increasingly selective. MRI-guided planning might be reserved for complex or anatomically challenging cases, whereas CT-based planning remains a robust and widely applicable standard.
Author Contributions
Conceptualization, Iustin-Mihai Pirsan and Johannes Knoth; Methodology, Johannes Knoth; Validation, Iustin-Mihai Pirsan, Alina E. Sturdza and Johannes Knoth; Formal analysis, Iustin-Mihai Pirsan and Aleksandra Winkler; Investigation, Iustin-Mihai Pirsan and Johannes Knoth; Data curation, Aleksandra Winkler and Claudia Gösenbauer; Writing – original draft, Iustin-Mihai Pirsan; Writing – review & editing, Iustin-Mihai Pirsan and Johannes Knoth; Visualization, Alina E. Sturdza and Johannes Knoth; Supervision, Alina E. Sturdza. Authorship must be limited to those who have contributed substantially to the work reported.
Funding
This research received no external funding.
Data Availability Statement
The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding author.
Abbreviations
The following abbreviations are used in this manuscript:
| LND | Lymph node dissection |
| SLNB | Sentinel lymph node biopsy |
| VBT | Vaginal cuff brachytherapy |
| MRI | Magnetic resonance imaging |
| CT | Computed tomography |
| OARs | Organs at risk |
| CTV | Clinical target volume |
References
- WHO. GLOBOCAN 2022 (2022) Estimated cancer incidence, mortality and prevalence worldwide in 2022. Available online: https://gco.iarc.fr/today/en/dataviz/bars?mode=population&cancers=24&populations=903_904_905_908_909_935.
- Concin, N.; Matias-Guiú, X.; Vergote, I. ESGO/ESTRO/ESP guidelines for the management of patients with endometrial carcinoma. Int. J. Gynecol. Cancer 2021, 31(1), 12–39. [Google Scholar] [CrossRef] [PubMed]
- Nout, R.A.; et al. Vaginal brachytherapy versus pelvic external beam radiotherapy for patients with endometrial cancer of high-intermediate risk (PORTEC-2): an open-label, non-inferiority, randomised trial. Lancet 2010, 375(9717), 816–23. [Google Scholar] [CrossRef] [PubMed]
- De Boer, S.M.; et al. Adjuvant chemoradiotherapy versus radiotherapy alone for women with high-risk endometrial cancer (PORTEC-3): final results of an international, open-label, multicentre, randomised, phase 3 trial. Lancet Oncol 2018. [Google Scholar] [PubMed]
- Viswanathan, A.N.; et al. Comparison and consensus guidelines for delineation of clinical target volume for CT- and MR- based brachytherapy in locally advanced cervical cancer. Int. J. Radiat. Oncol. Biol. Phys. 2014, 90(2), 320–8. [Google Scholar] [CrossRef] [PubMed]
- Rakhra, S.S.; et al. The effect of pelvic radiotherapy on vaginal brachytherapy cylinder diameter: Implications for optimal treatment order. Brachytherapy 2016, 15(5), 549–53. [Google Scholar] [CrossRef] [PubMed]
- Ozdemir, Y.; et al. Effects of vaginal cylinder position on dose distribution in patients with endometrial carcinoma in treatment of vaginal cuff brachytherapy. J. Contemp. Brachytherapy 2017, 9(3), 230–235. [Google Scholar] [CrossRef] [PubMed]
- Bahadur, Y.A.; et al. Single versus multichannel applicator in high-dose-rate vaginal brachytherapy optimized by inverse treatment planning. J. Contemp. Brachytherapy 2015, 6(4), 362–70. [Google Scholar] [PubMed]
- Rovirosa, A.; et al. Can we shorten the overall treatment time in postoperative brachytherapy of endometrial carcinoma? Comparison oft wo brachytherapy schedules. Radiother. Oncol. 2015, 116(1), 143–8. [Google Scholar] [CrossRef] [PubMed]
- Owrangi, A.M.; et al. Clinical implementation of MR-guided vaginal cylinder brachytherapy. J. Appl. Clin. Med. Phys. 2015, 16(6), 490–500. [Google Scholar] [CrossRef] [PubMed]
- Gebhardt, B.; et al. Image-guided tandem and cylinder brachytherapy as monotherapy for definitive treatment of inoperable endometrial carcinoma. Gynecol. Oncol. 2017, 147(2), 302–308. [Google Scholar] [CrossRef] [PubMed]
- Jordan, S.E.; et al. Image-guided high-dose-rate intracavitary brachytherapy in the treatment of medically inoperable early-stage endometrioid type endometrial adenocarcinoma. Brachytherapy 2017, 16(6), 1144–1151. [Google Scholar] [PubMed]
- Chapman, C.H.; et al. MRI-Based Evaluation of the Vaginal Cuff in Brachytherapy Planning: Are We Missing the Target? Int. J. Radiat. Oncol. Biol. Phys. 2016, 95(2), 743–50. [Google Scholar] [CrossRef] [PubMed]
- Van den Heerik, et al. PORTEC-4a: international randomized trial of molecular profile-based adjuvant treatment for women with high-intermediate risk endometrial cancer. Int. J. Gynecol. Cancer 30(Issue 12), 2002–2007. [PubMed]
- León-Castillo, A.; et al. Pattern of recurrence of the molecular subgroups in stage I high-grade endometrial cancer. Gynecol. Oncol. 2025, 197, 43–50. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Example of a cylinder applicator with the diameter of 35 mm and length of 7,5 cm.

Figure 2.
Clinical workflow.
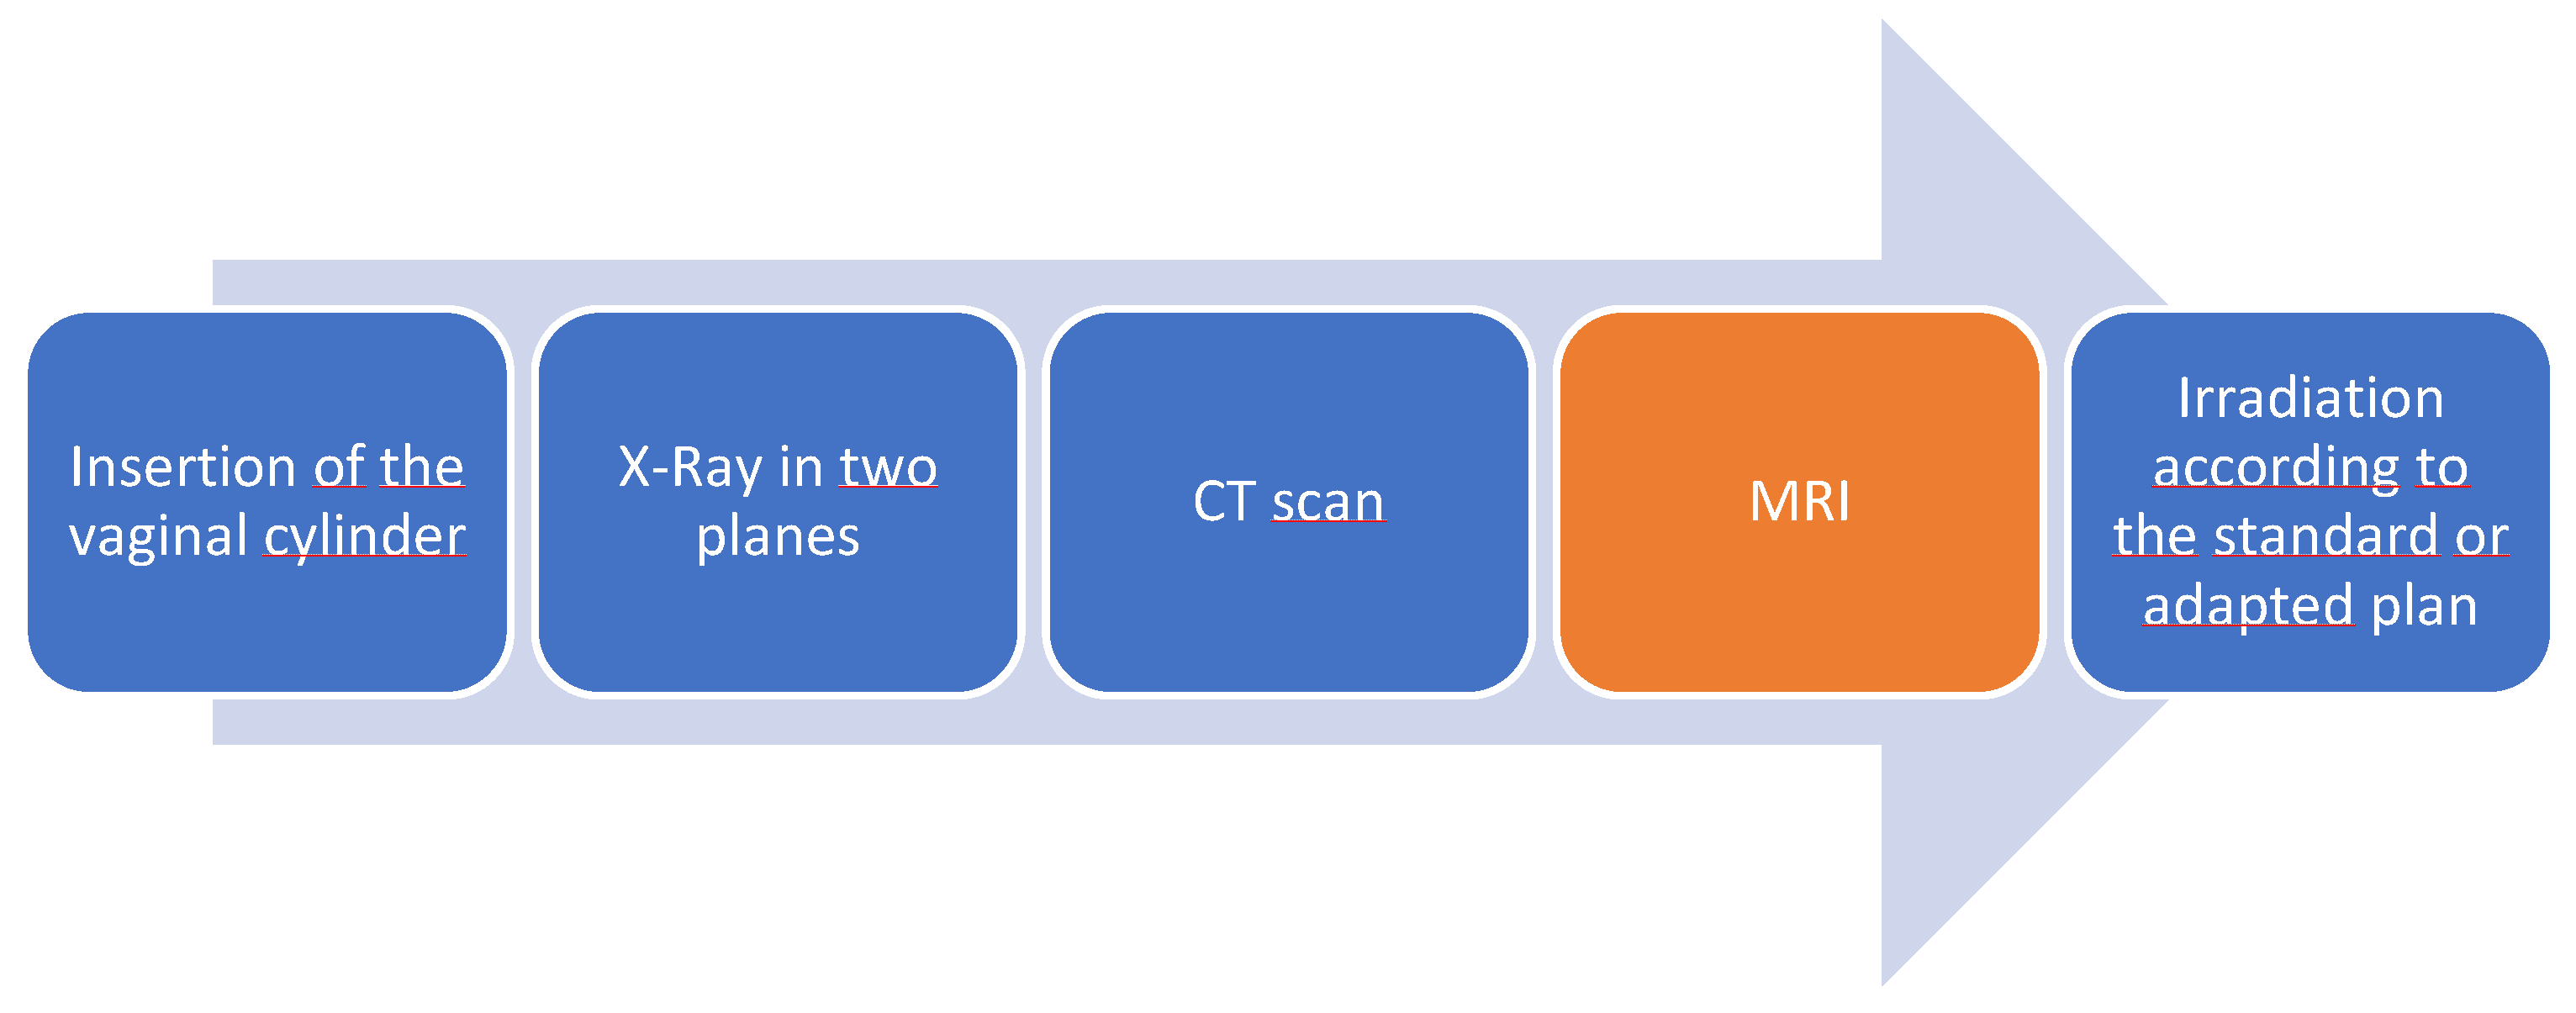
Figure 3.
CT and MRI contouring: axial, sagittal, and coronal CT images (top row) and corresponding MRI images (bottom row) of a representative patient. The clinical target volume (CTV) contours differ slightly between the two modalities, with MRI demonstrating a slightly smaller CTV volume compared to CT.
Figure 3.
CT and MRI contouring: axial, sagittal, and coronal CT images (top row) and corresponding MRI images (bottom row) of a representative patient. The clinical target volume (CTV) contours differ slightly between the two modalities, with MRI demonstrating a slightly smaller CTV volume compared to CT.
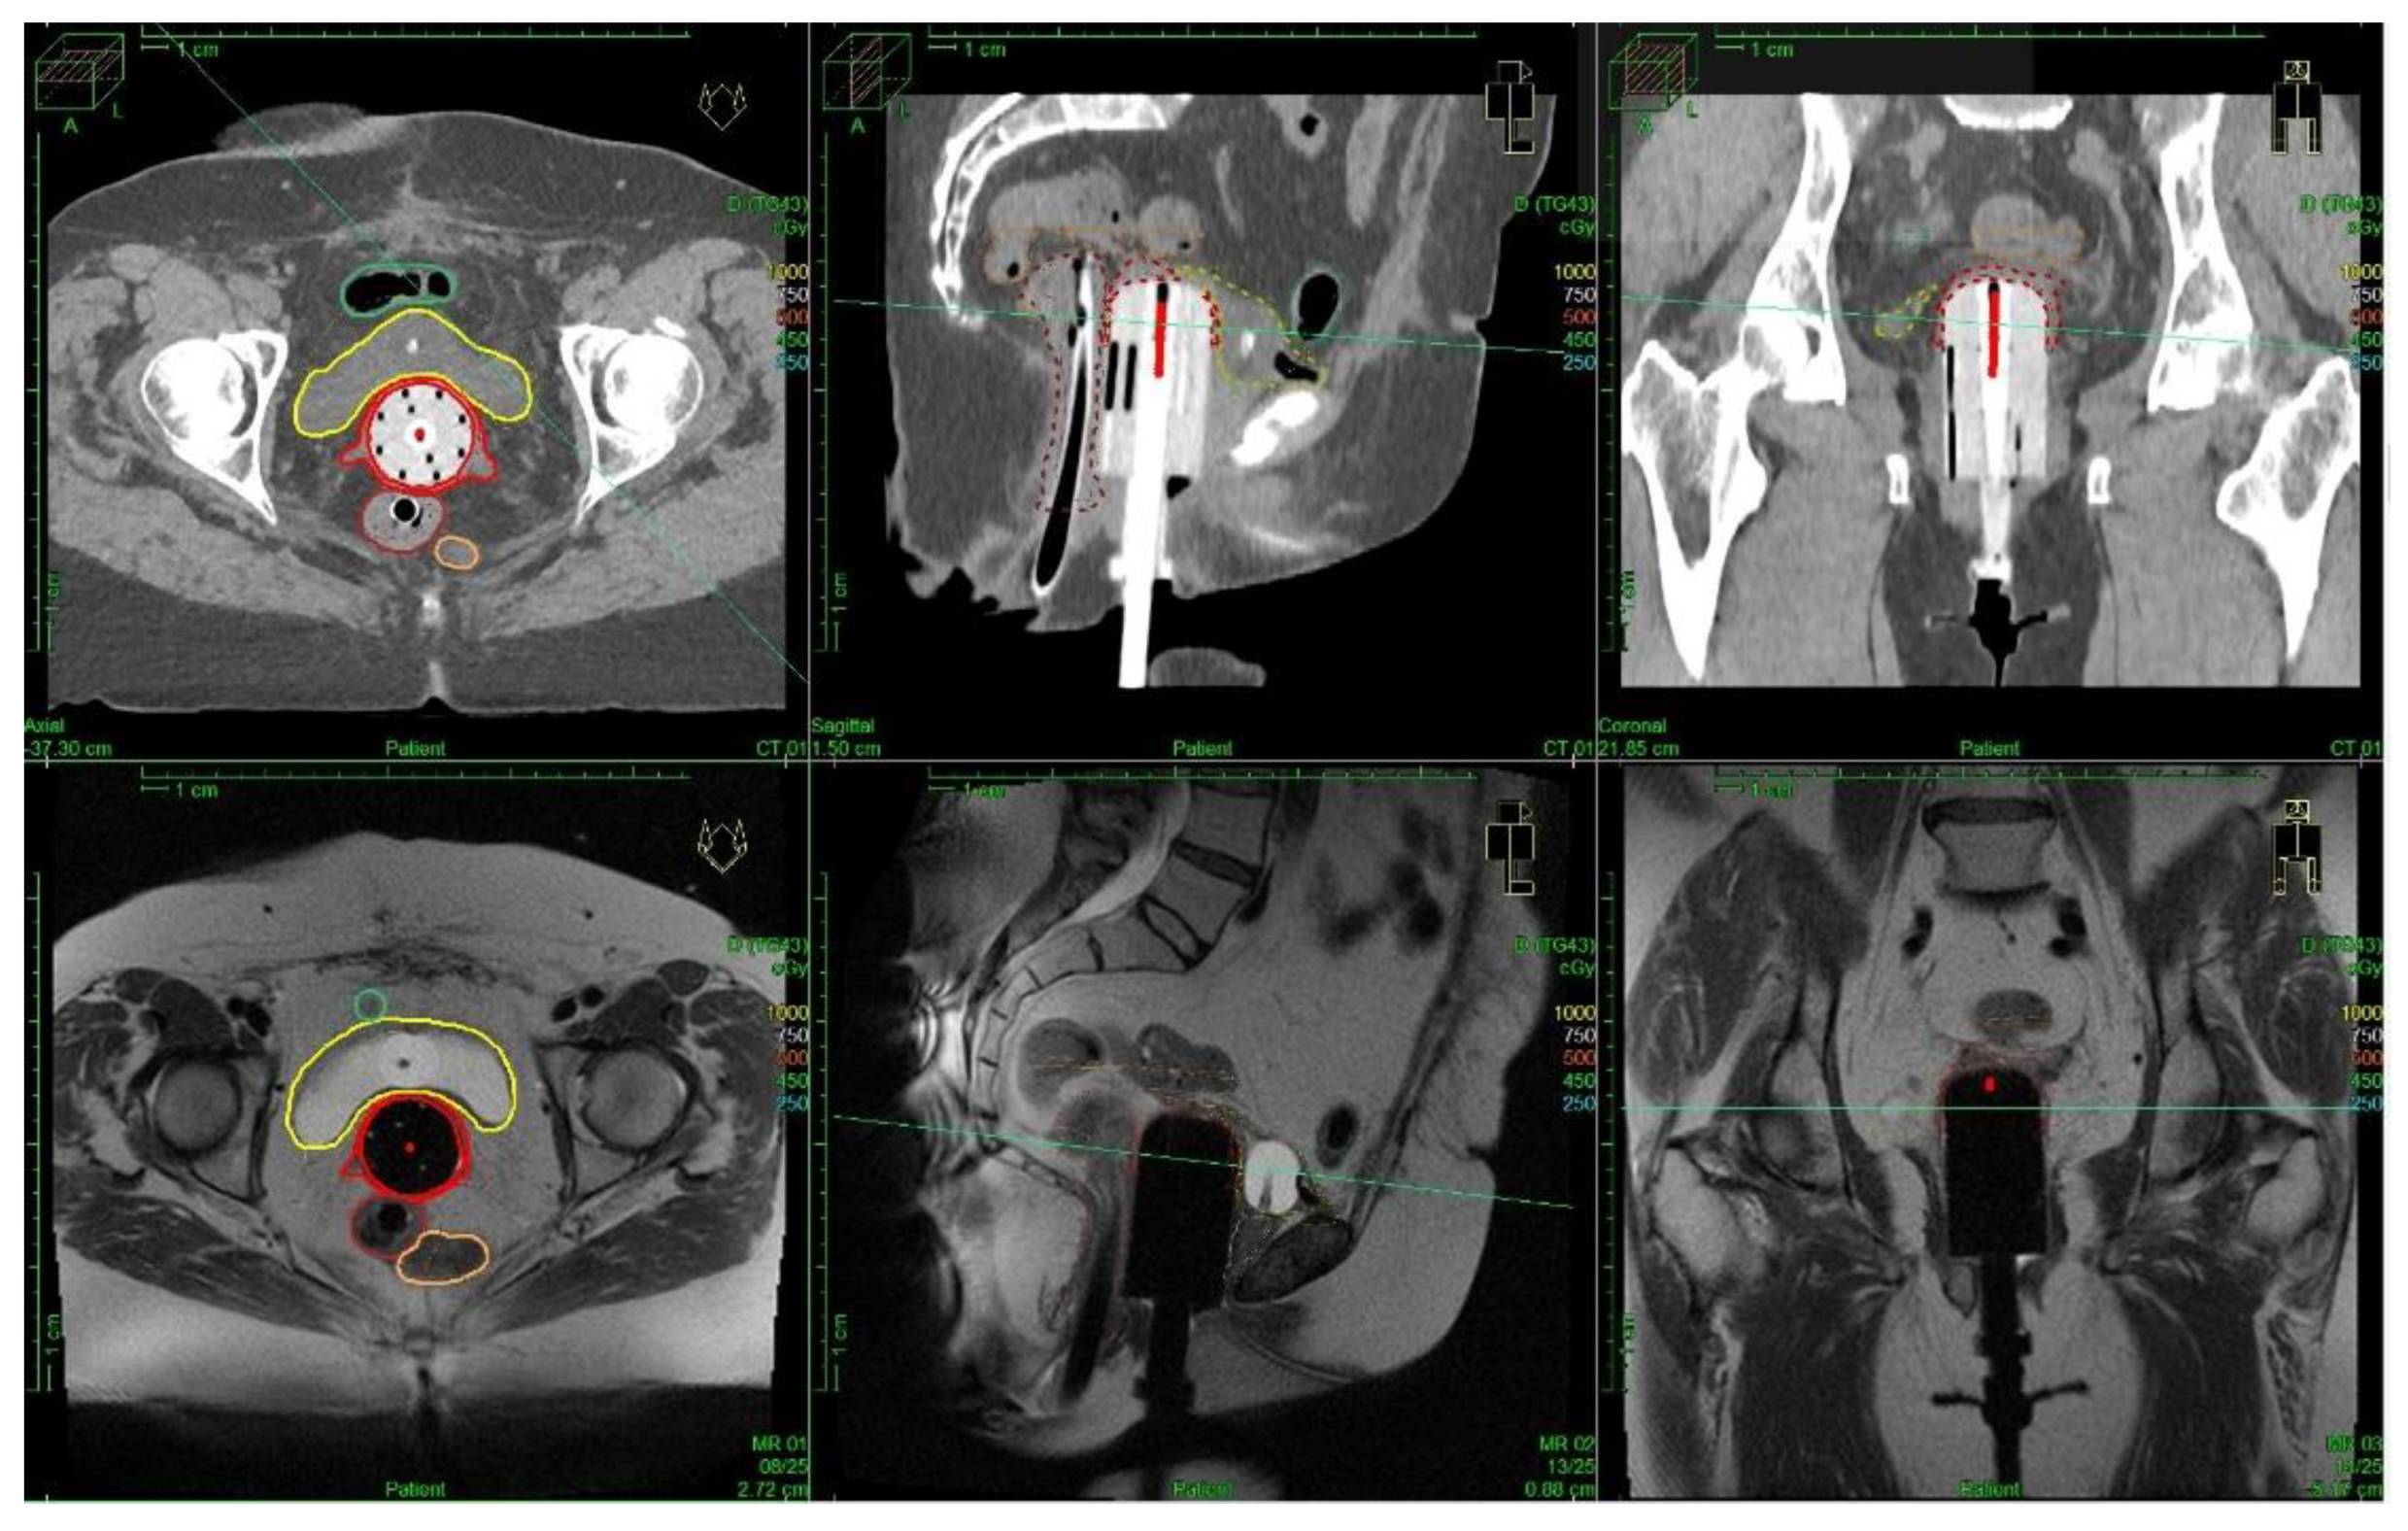

Table 1.
Patient and treatment characteristics (n = 25). Abbreviations: LND = lymph node dissection; SLNB = sentinel lymph node biopsy; G = tumor grade; L = lymphatic invasion; V = vascular invasion; R0 = microscopically negative resection margin; VBT = vaginal cuff brachytherapy.
Table 1.
Patient and treatment characteristics (n = 25). Abbreviations: LND = lymph node dissection; SLNB = sentinel lymph node biopsy; G = tumor grade; L = lymphatic invasion; V = vascular invasion; R0 = microscopically negative resection margin; VBT = vaginal cuff brachytherapy.
| Characteristic | n (%) |
|---|---|
| Age at diagnosis (years) | Median 65 (range 51–80) |
| T stage | T1a: 7 (28%) T1b: 9 (36%) T2: 7 (28%) T3a: 2 (8%) |
| N stage | N0: 23 (92%) N1: 1 (4%) Nx: 1 (4%) |
| Lymph node sampling | LND: 12 (48%) Sentinel: 11 (44%) None: 2 (8%) |
| Histology | Endometrioid: 16 (63%) Serous/papillary: 3 (12%) Carcinosarcoma: 3 (12%) Mixed: 2 (8%) Clear cell: 1 (5%) |
| Grading | G1: 2 (8%) G2: 6 (24%) G3: 13 (52%) Unknown: 4 (16%) |
| Lymphovascular invasion (L) | L1: 2 (8%) L0: 23 (92%) |
| Vascular invasion (V) | V1: 1 (4%) V0: 24 (96%) |
| Resection margin (R) | R0: 20 (80%) Unknown: 5 (20%) |
Table 2.
CTV Volumes and Dosimetric Parameters (MRI vs CT, dose per fraction, n = 25).
| Parameter | MRI (mean ± SD) | CT (mean ± SD) | p-value |
| CTV volume (cm³) | 10.9 ± 5.4 | 13.9 ± 5.9 | 0.00035* |
| EQD2 D90 (Gy) | 5.32 ± 1.84 | 5.10 ± 1.59 | 0.433 |
| EQD2 D98 (Gy) | 3.95 ± 1.55 | 3.80 ± 1.40 | 0.491 |
| EQD2 D50 (Gy) | 9.12 ± 1.27 | 8.62 ± 1.34 | 0.012* |
*Statistically significant (p < 0.05).
Table 3.
OARs D2cm³ doses in EQD2 (MRI vs CT, n=25).
| Organ | MRI mean (Gy) | CT mean (Gy) | Mean Δ (Gy) | p-value |
|---|---|---|---|---|
| Bladder | 7.6 | 7.4 | +0.2 | 0.44 |
| Rectum | 6.3 | 6.3 | +0.0 | 0.87 |
| Sigmoid | 3.2 | 3.2 | +0.0 | 0.97 |
| Bowel | 4.0 | 3.9 | +0.1 | 0.81 |
| Urethra | 2.3 | 2.5 | –0.2 | 0.11 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.