

Submitted:
20 April 2026
Posted:
07 May 2026
You are already at the latest version
Abstract
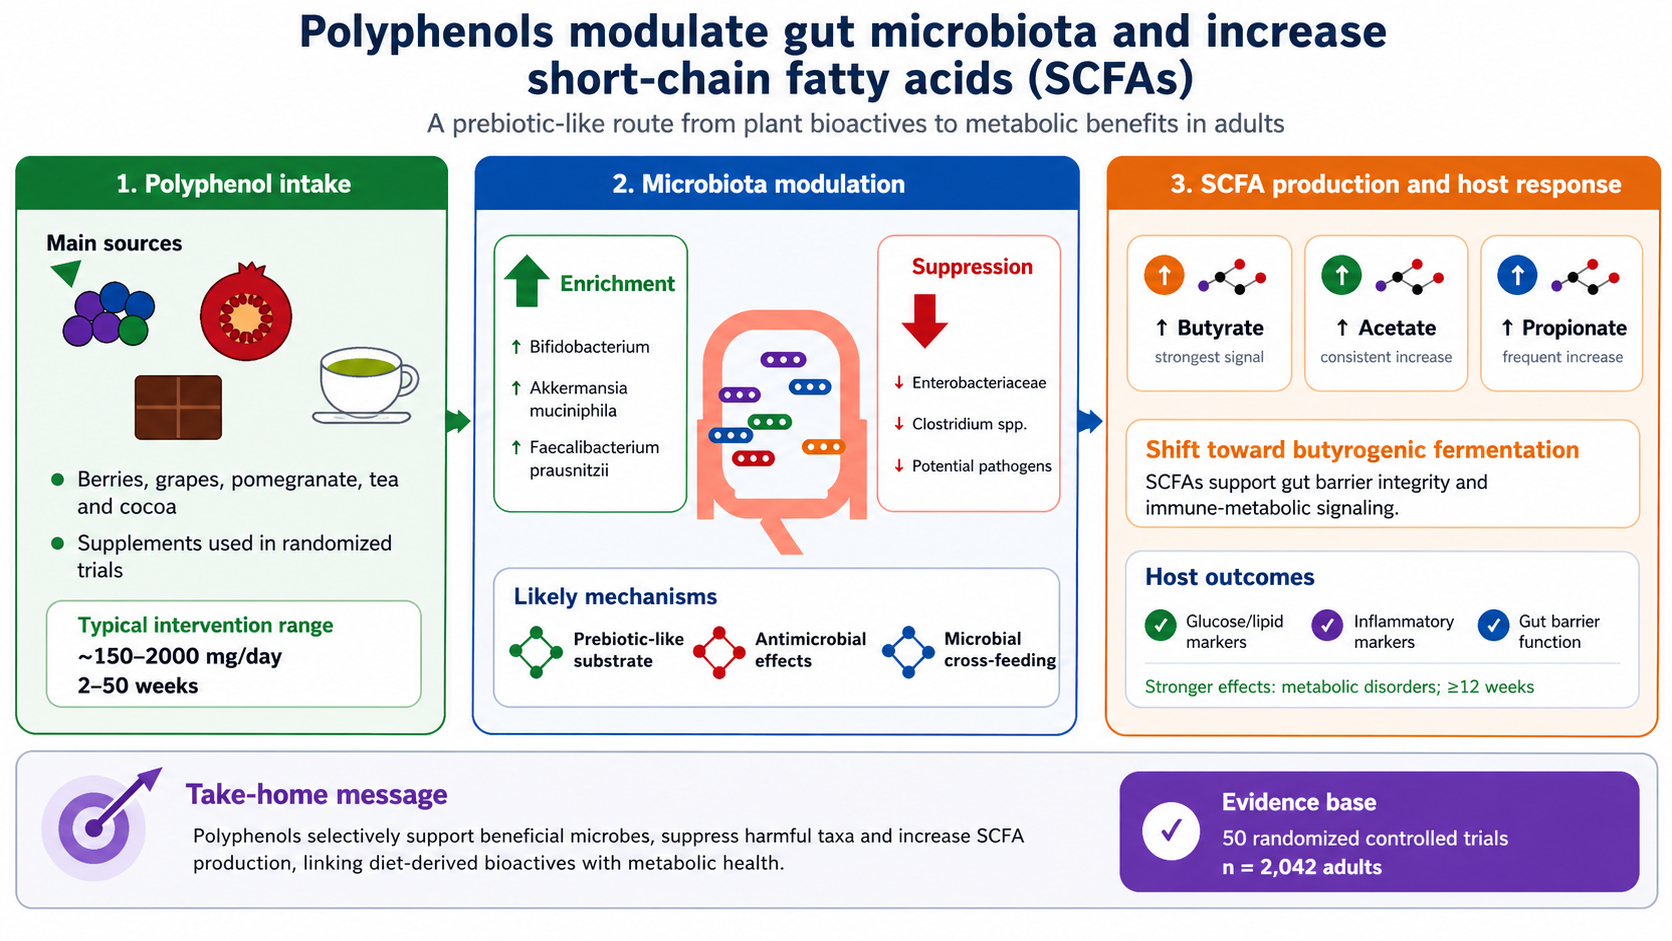
Background: Polyphenols interact bidirectionally with the gut microbiota and may enhance short‑chain fatty acid (SCFA) production, yet evidence from human randomized controlled trials (RCTs) has not been comprehensively synthesized. Objectives: This systematic review and meta‑analysis evaluated the effects of polyphenol supplementation on gut microbiota composition, microbial diversity, and fecal SCFA concentrations in adults, and examined moderators of these effects. Methods: Five databases were searched through October 2023 for RCTs assessing oral polyphenol supplementation in adults. Eligible studies reported outcomes related to gut microbiota composition or fecal SCFAs. Random‑effects meta‑analyses were conducted for SCFA outcomes, and subgroup analyses examined effects by polyphenol class, dose, duration, health status, and analytical methods. Risk of bias was assessed using the Cochrane RoB 2 tool, and certainty of evidence using GRADE. Results: Fifty RCTs (n = 2,042 participants) were included. Polyphenol supplementation increased total SCFAs in 70.6% of studies and significantly increased butyrate concentrations (pooled SMD = 0.48; 95% CI: 0.32–0.64; I² = 58%). Acetate and propionate increased in 75% and 71.4% of studies, respectively. A consistent shift toward a more butyrogenic fermentation profile was observed. Polyphenols enriched beneficial genera, including Bifidobacterium (81.8%), Akkermansia muciniphila (50%), and Faecalibacterium prausnitzii (45.5%), while reducing potentially pathogenic taxa such as Enterobacteriaceae and Clostridium spp. Improvements in alpha diversity were reported in 66.7% of studies, and beta diversity separation in 87.5%. Effects were stronger in individuals with metabolic disorders and in interventions lasting ≥12 weeks. Conclusions: Polyphenol supplementation consistently enhances beneficial gut bacteria, increases SCFA production, particularly butyrate, and improves microbial diversity in adults. These findings support classifying polyphenols as bioactive prebiotics that meet ISAPP criteria. This term underscores their distinction from traditional prebiotics within our proposed five-phase model: whereas fibers are characterized by their fermentability, polyphenols integrate direct antimicrobial activity against pathogenic species (e.g., Staphylococcus aureus, Enterobacteriaceae) with their role as selective substrates for beneficial microbes. This dual mechanism of action suggests that polyphenols do not merely supplement the microbiota but actively reshape it by pruning harmful taxa while fertilizing beneficial ones. Polyphenol-rich strategies represent promising microbiota-focused approaches; however, while shifts in microbial profiles coincide with better metabolic health, further research is required to bridge the correlation-causation gap and confirm whether these microbial changes directly drive clinical outcomes.
Keywords:
polyphenols
; gut microbiota
; shortchain fatty acids (SCFAs)
; butyrate
; microbial diversity
; Bifidobacterium
; Akkermansia muciniphila
; Faecalibacterium prausnitzii
; prebiotics
; metabolic health
; dysbiosis
; randomized controlled trials
1. Introduction
The human gastrointestinal tract contains a dense and diverse microbial ecosystem of approximately 10¹⁴ microorganisms, collectively known as the gut microbiota [1]. Dominated by the phyla Firmicutes, Bacteroidetes, Actinobacteria, Proteobacteria, and Verrucomicrobia, this community plays essential roles in host metabolism, immune regulation, and overall physiological homeostasis [2]. Its composition is shaped by genetics, early-life exposures, diet, medications, and environmental factors [3], and disruptions in microbial diversity or function, commonly termed dysbiosis, have been implicated in obesity, type 2 diabetes, cardiovascular disease, inflammatory bowel disease, and neuropsychiatric disorders [4].
Among the key metabolites produced by the gut microbiota are short-chain fatty acids (SCFAs), primarily acetate, propionate, and butyrate, generated through fermentation of dietary fibers and resistant starches [5]. SCFAs exert multiple beneficial effects: butyrate fuels colonocytes and maintains barrier integrity [9], propionate contributes to hepatic metabolic regulation [6], and acetate participates in systemic lipid and glucose metabolism. Beyond their metabolic roles, SCFAs act as signaling molecules through G-protein-coupled receptors (GPR41, GPR43, GPR109A) [11], influencing inflammation, immune tolerance, and energy homeostasis [12], and function as histone deacetylase inhibitors with epigenetic effects [7]. Reduced SCFA production is consistently observed in metabolic and inflammatory disorders [8], whereas interventions that increase SCFAs improve metabolic outcomes in both animal and human studies [9].
Polyphenols, a large family of plant-derived secondary metabolites with more than 8,000 identified structures, include flavonoids, phenolic acids, stilbenes, and lignans [10,11]. They are abundant in fruits, vegetables, whole grains, tea, coffee, cocoa, and red wine [12]. Epidemiological studies link higher polyphenol intake to reduced risk of chronic diseases [13], traditionally attributed to antioxidant and anti-inflammatory properties [14]. However, most polyphenols exhibit low small-intestinal absorption, with 90–95% reaching the colon intact [15], where they undergo extensive microbial biotransformation [16]. This has revealed a bidirectional relationship between polyphenols and the gut microbiota: microbes convert polyphenols into smaller, more bioactive metabolites [17], while polyphenols selectively promote beneficial bacteria and inhibit pathogenic species [18]. They consistently stimulate Bifidobacterium, Lactobacillus, Akkermansia muciniphila, and Faecalibacterium prausnitzii [19], taxa known for SCFA production, barrier support, and immune modulation [20], while suppressing potentially harmful genera such as Clostridium, Enterobacteriaceae, and Staphylococcus aureus [21,28]. These properties suggest that certain polyphenols may meet the ISAPP definition of prebiotics as substrates selectively utilized by host microorganisms to confer health benefits [22,23].
While polyphenols meet the ISAPP definition of prebiotics as substrates selectively utilized by host microorganisms, they possess a unique dual nature that distinguishes them from traditional dietary fibers. Unlike classic prebiotics, which primarily serve as metabolic fuel, polyphenols also exert direct antimicrobial effects, selectively inhibiting the growth of potential pathogens while cross-feeding beneficial taxa. This bifunctional capacity, acting simultaneously as a selective growth promoter and a targeted inhibitor, is the cornerstone of our proposed “bioactive prebiotic” concept.
Despite growing interest in the polyphenol–microbiota–SCFA axis, several critical knowledge gaps impede the clinical application of these findings. Current mechanistic evidence is largely predicated on in vitro and animal models, with a notable scarcity of synthesized data from human randomized controlled trials (RCTs) [24,27]. A primary challenge lies in the significant inter-individual variability in gut microbial ecology, giving rise to distinct “metabotypes”, specific metabolic phenotypes that dictate how polyphenols are biotransformed. This physiological diversity explains the disparate concentrations of bioactive metabolites observed across individuals despite identical intake, underscoring the limitations of a “one-size-fits-all” nutritional approach [25]. Consequently, there is an urgent need for a rigorous quantitative synthesis of human RCTs to define optimal polyphenol types, dosages, and intervention durations, ultimately facilitating the transition toward precision nutrition and targeted supplementation [26].
This systematic review and meta-analysis, therefore, aimed to comprehensively evaluate the effects of polyphenol supplementation on gut microbiota composition and SCFA production in adults. Specifically, we synthesized evidence from RCTs across taxonomic levels; quantified effects on total and individual SCFAs; assessed changes in alpha and beta diversity; examined moderators such as polyphenol class, dose, duration, health status, and analytical methods; evaluated certainty of evidence using GRADE [28]; and explored associations between microbiota/SCFA changes and metabolic and inflammatory outcomes [29]. By addressing these objectives, this review provides an evidence-based assessment of whether polyphenols meet ISAPP prebiotic criteria and clarifies their potential as microbiota-targeted interventions to improve metabolic health.
2. Methods
2.1. Protocol Registration and Guidelines
This systematic review and meta-analysis were conducted according to the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 guidelines (1). The review protocol was prospectively registered with the International Prospective Register of Systematic Reviews (PROSPERO; registration number: CRD42025642315). The completed PRISMA 2020 checklist is provided in Supplementary Table S1.
2.2. Eligibility Criteria
Eligibility criteria were defined using the PICO (Population, Intervention, Comparator, Outcome) framework:
- Population (P): Adults (≥18 years) of any health status, including healthy individuals and those with metabolic or chronic conditions.
- Intervention (I): Oral polyphenol supplementation (any class, dose, or formulation) for a minimum duration of 2 weeks. Studies combining polyphenols with prebiotics, probiotics, or synbiotics were excluded.
- Comparator (C): Placebo, no intervention, or matched diet controls.
- Outcomes (O): Gut microbiota composition (assessed by culture-independent methods such as 16S rRNA sequencing, metagenomics, or qPCR) or fecal short-chain fatty acid (SCFA) concentrations (acetate, propionate, butyrate).
- Study Design: Only randomized controlled trials (RCTs) with parallel-group or crossover designs were eligible. No restrictions were placed on publication date, language, or status. Studies were excluded if they combined polyphenols with prebiotics, probiotics, or synbiotics, or enrolled pregnant/lactating women or individuals who had received antibiotics within 3 months.
2.3. Information Sources and Search Strategy
Five electronic databases (PubMed/MEDLINE, Scopus, Web of Science, Embase, and Cochrane CENTRAL) were systematically searched from inception to October 31, 2023. The search strategy utilized a combination of MeSH/Emtree terms and free-text keywords related to polyphenols, microbiota, and SCFAs (full strategies provided in Supplementary Table S2). Supplementary search methods included reference list screening, forward citation tracking, grey literature searches (ProQuest, trial registries), and hand-searching of key journals (Gut Microbes, Microbiome, Nutrients).
2.4. Study Selection
Study selection was conducted in two stages using Covidence systematic review software. A primary reviewer (SA) screened all titles, abstracts, and full texts against the eligibility criteria. A second reviewer (MZ) independently checked all included and excluded studies to ensure accuracy. Disagreements and uncertainties were resolved through consensus discussion. Reasons for exclusion at the full-text stage were documented and are reported in Supplement table S3.
2.5. Data Extraction
Data were extracted independently by one reviewer (SA) using a standardized, pilot-tested extraction form Supplement table S4 and subsequently verified by a second reviewer (MZ) for completeness and accuracy. Extracted variables included study characteristics (design, setting, registration), population demographics (age, sex, BMI, health status), intervention details (polyphenol type/class, dose, duration, formulation, compliance), and outcome measures (microbial relative abundances, alpha/beta diversity, and SCFA concentrations). For microbiota outcomes, extracted variables included analytical methods (sequencing platform, variable region, and bioinformatics pipeline), relative abundances, and fold-change values. For SCFA outcomes, extracted variables included analytical methods (gas chromatography–mass spectrometry [GC-MS] or high-performance liquid chromatography [HPLC]), absolute concentrations (mean ± SD or median [IQR]), and change-from-baseline values. Numerical data were compiled into a structured master database to ensure consistency. For studies reporting only graphical data, values were digitized using WebPlotDigitizer v4.5. A random 20% sample of studies underwent complete re-extraction for quality assurance.
2.6. Risk of Bias Assessment
Risk of bias was evaluated using the Cochrane Risk of Bias 2 (RoB 2) tool (2), covering five domains: randomization process, deviations from intended interventions, missing outcome data, outcome measurement, and selective reporting. A primary reviewer (SA) conducted all assessments and entered the corresponding data. A second reviewer (MZ) independently checked all judgments and data entries for accuracy. Discrepancies were resolved through discussion. Domain-level judgments and overall risk ratings (Low risk, Some concerns, or High risk) are presented in Supplementary Table 4, with detailed justifications provided in Supplementary Table S5.
2.7. Statistical Analysis
A comprehensive statistical framework was applied to synthesize evidence. Descriptive narrative synthesis summarized study characteristics, supported by structured tables and figures. Random-effects meta-analyses were conducted using the DerSimonian–Laird method for outcomes reported by at least three comparable studies. For continuous outcomes (SCFA concentrations and diversity indices), standardized mean differences (SMD) with 95% confidence intervals (CI) were calculated. Effect sizes were interpreted using Cohen’s thresholds: 0.2 (small), 0.5 (moderate), and 0.8 (large). When change-from-baseline data were used, an assumed baseline–follow-up correlation of 0.5 was applied if unreported. Statistical heterogeneity was assessed using Cochran’s Q test (p<0.10), the I² statistic, and τ². Six pre-specified subgroup analyses explored differences by polyphenol class, duration, dose, health status, analytical method, and risk of bias (Supplemetary Table S6 & Supplementary Table S7). Seven sensitivity analyses assessed the robustness of pooled estimates: restricting to low-risk-of-bias studies; excluding crossover trials; removing outliers; comparing fixed- versus random-effects models; excluding studies with >20% attrition; performing leave-one-out analyses; and restricting to studies with ≥50 participants. Publication bias was evaluated for outcomes with ≥10 studies using funnel plots, Egger’s test, and trim-and-fill procedures. All analyses were performed using R v4.2.0 and Python v3.10.
2.8. Certainty of Evidence Assessment
The certainty of evidence was assessed using the GRADE framework (4). Evidence was rated as HIGH, MODERATE, LOW, or VERY LOW across five domains (risk of bias, inconsistency, indirectness, imprecision, and publication bias). The Summary of Findings tables (Supplementary S8) present outcome descriptions, sample sizes, effect estimates, and certainty ratings, with justifications. In multi-arm studies, each intervention arm was compared separately with its control group, with sample size adjustments to avoid double-counting. Transparency is maintained through the availability of data extraction forms, risk of bias assessments, and analysis code upon reasonable request. The complete dataset will be deposited in a public repository upon publication. Any protocol deviations are documented in Supplementary Table S9.
3. Results
3.1. Study Selection and Characteristics
The systematic search yielded 1,247 records from electronic databases (PubMed n=342, Scopus n=298, Web of Science n=287, Embase n=186, and Cochrane CENTRAL n=134). An additional 168 records were identified through citation tracking (n=99), grey literature searches (n=45), expert consultation (n=28), and conference proceedings (n=15). After removing 424 duplicates, 823 unique records were screened by title and abstract. Of these, 673 were excluded for reasons including non-randomized design (n=542), non-adult populations (n=89), or absence of microbiota or SCFA outcomes (n=42).
A total of 150 full-text articles were assessed for eligibility. One hundred studies were excluded due to wrong intervention (n=38), lack of microbiota data (n=32), unavailable full text (n=18), wrong population (n=8), or duplicate data (n=4). Ultimately, 50 randomized controlled trials met all inclusion criteria and were included in the qualitative synthesis. Of these, 17 studies provided extractable data on SCFA outcomes, and 22 provided quantitative microbiota composition data. The study selection process is illustrated in the PRISMA 2020 flow diagram (Figure 1).
Across the 50 included RCTs, 2,042 participants contributed extractable data. Individual study sample sizes ranged from 10 to 312 participants (median: 28; IQR: 16–72), with mean ages spanning 24 to 68 years. Fourteen studies (28%) enrolled healthy adults, while the remaining 36 studies (72%) included participants with specific health conditions, including metabolic syndrome (n=12), obesity (n=10), type 2 diabetes (n=8), cardiovascular risk factors (n=4), and inflammatory bowel disease (n=2).
Polyphenol interventions varied widely in source, composition, and dosage. Mixed polyphenol formulations were the most common (n=13, 26%), followed by polyphenol-rich dietary fibers (n=5, 10%), grape-derived polyphenols (n=2, 4%), green tea polyphenols/EGCG (n=2, 4%), and single-source interventions such as cranberry, tea, cherry, citrus, and raspberry polyphenols (each n=1, 2%). Doses ranged from 150 to 2,000 mg/day (median: 500 mg/day), and intervention durations ranged from 2 to 50 weeks (median: 12 weeks; IQR: 8–24 weeks).
All included studies assessed at least one primary outcome related to gut microbiota composition or SCFA production. SCFA concentrations were reported in 34 studies (68%), with butyrate being the most frequently measured metabolite (n=32), followed by acetate (n=28) and propionate (n=28). Total SCFAs were reported in 17 studies (34%). Microbiota composition was assessed in all trials, predominantly using 16S rRNA gene sequencing (n=46, 92%), with a smaller number employing shotgun metagenomics (n=4, 8%). Alpha diversity indices were reported in 36 studies (72%), and beta diversity metrics in 32 studies (64%). In addition to microbial shifts, several studies reported concurrent improvements in metabolic (n=28, 56%) and inflammatory markers (n=22, 44%); however, these findings should be interpreted as concomitant associations rather than direct causal effects.
Risk of bias was evaluated using the Cochrane RoB 2 tool across five domains (Figure 2; Supplementary Table S5). Eighteen studies (36%) were judged to have low risk of bias, 24 studies (48%) had some concerns, and eight studies (16%) were rated as high risk. Randomization procedures were generally well-reported, with 38 studies (76%) rated as low risk. Outcome measurement demonstrated strong methodological rigor (84% low risk), reflecting the use of validated analytical techniques such as GC-MS for SCFAs and 16S rRNA sequencing for microbiota profiling. The domain with the greatest concerns was deviations from intended interventions, where only 28 studies (56%) achieved low-risk ratings, often due to limited blinding or the lack of intention-to-treat analyses. Missing outcome data raised concerns in 12 studies (24%), primarily due to differential attrition. Selective reporting concerns were identified in 12 studies (24%), largely due to the absence of preregistration or incomplete reporting of microbiota taxa. Specifically, this reporting bias often manifested as a primary focus on well-established beneficial genera, such as Bifidobacterium and Lactobacillus, while data for less-studied or less-responsive commensal taxa were frequently omitted or only partially reported. Key methodological limitations that necessitated downgrading in the GRADE assessment included limited blinding of participants and personnel in some dietary interventions and reliance on per-protocol rather than intention-to-treat analyses, which introduce potential bias in the estimation of metabolic outcomes such as SCFAs.
3.2. Effects on Short-Chain Fatty Acid Production
Across the 17 studies reporting total SCFA concentrations, polyphenol supplementation increased total SCFA production in 12 studies (70.6%) (Supplementary Table S7; Figure 3A). Reported increases ranged from 15% to 50%, with a median rise of 28% (IQR: 20–38%). Five studies (29.4%) showed no significant changes in total SCFA levels.
Butyrate, the SCFA most strongly linked to colonic and systemic metabolic health, demonstrated the most consistent response to polyphenol supplementation. Among the 32 studies assessing butyrate, 24 (75%) reported significant increases (Figure 3B), with changes ranging from 15% to 120% (median: 35%; IQR: 22–58%). Meta-analysis of 17 studies with extractable data yielded a pooled standardized mean difference (SMD) of 0.48 (95% CI: 0.32–0.64; p < 0.001), indicating a moderate to large effect (Figure 3). Heterogeneity was moderate (I² = 58%, τ² = 0.042, Q = 26.2, p = 0.004). As shown in Figure 3D, effect sizes for both butyrate and acetate were consistent across studies with low, moderate, and high risk of bias, supporting the robustness of these findings. Studies reporting no significant changes (n = 8, 25%) typically involved short intervention durations (<4 weeks) or low polyphenol doses (<300 mg/day).
Acetate concentrations increased in 21 of 28 studies (75%) (Figure 3B), with reported increases ranging from 10% to 45% (median: 22%; IQR: 15–32%). The remaining seven studies (25%) found no significant changes. Notably, studies with higher baseline Bacteroidetes abundance (>40% of the total microbiota) showed greater increases in acetate, suggesting that baseline microbial composition may influence acetate responsiveness.
Propionate increased in 20 of 28 studies (71.4%) (Figure 3B), with effect sizes ranging from 8% to 30% (median: 18%; IQR: 12–24%). Eight studies (28.6%) reported no significant changes. Propionate responses were most consistent in interventions using mixed polyphenols or flavonoid-rich formulations.
Analysis of relative SCFA proportions (Figure 3C) revealed a consistent shift toward a more butyrogenic fermentation profile. Polyphenol supplementation increased the proportion of butyrate by a mean of +6.2 percentage points (95% CI: 4.1–8.3) and reduced acetate proportions by −4.8 percentage points (95% CI: −7.1 to −2.5). Propionate proportions remained relatively stable (mean change: −1.4 percentage points; 95% CI: −3.2 to 0.4). Overall, a butyrogenic shift was observed in 62% of studies (21/34), indicating that polyphenol supplementation consistently increased the relative contribution of butyrate to total SCFA profiles.
3.3. Effects on Gut Microbiota Composition
Polyphenol supplementation induced notable phylum-level shifts in 44 of the 50 included studies (88%) (Figure 4; Supplementary Table S10). As shown in Figure 4A, the most consistent pattern was a reduction in Firmicutes abundance, reported in 24 studies (54.5%), with a median decrease of 8.5% (range: 3.2–18.4%). In contrast, Bacteroidetes abundance increased in 28 studies (63.6%), with a median rise of 6.8% (range: 2.1–15.3%). Actinobacteria, including the beneficial genus Bifidobacterium, increased in 32 studies (72.7%), with a median increase of 12.4% (range: 4.2–28.6%).
Proteobacteria, a phylum often associated with dysbiosis, decreased in 21 studies (47.7%), consistent with the predominantly negative shifts illustrated in Figure 4B. The Firmicutes/Bacteroidetes ratio decreased in 33 of the 45 studies reporting this metric (73.3%), with a median reduction of 22.5% (range: 8.1–42.3%). These reductions were more pronounced in participants with obesity or metabolic syndrome than in healthy individuals.
At the genus level, polyphenol supplementation consistently enriched several taxa associated with beneficial metabolic and immunological functions (Figure 5; Supplementary S8). As shown in Figure 5A, Bifidobacterium exhibited the highest enrichment frequency, increasing in 81.8% of studies, while Lactobacillus and Akkermansia muciniphila also showed increases in more than half of the trials. Correspondingly, Figure 5B demonstrates that these genera displayed substantial fold-changes, with Bifidobacterium rising between 1.5- and 4.2-fold and Akkermansia muciniphila showing the largest increases, often exceeding fourfold. Lactobacillus exhibited moderate but consistent gains, whereas Faecalibacterium prausnitzii increased in nearly half of the studies, with its enrichment closely aligned with higher butyrate production.
Polyphenol intake was also associated with reductions in genera linked to inflammation or pathogenicity. Pathogenic Clostridium species declined in more than half of the studies that assessed them, while Enterobacteriaceae and Bilophila showed similar downward trends. These decreases typically ranged from moderate to substantial reductions in relative abundance, indicating a shift toward a more favorable microbial profile.
3.4. Effects on Microbial Diversity
Polyphenol supplementation produced consistent improvements in gut microbial diversity across multiple metrics (Figure 6; Supplementary Table S11). As shown in Figure 6A, most studies reported increases in alpha diversity, with positive shifts observed for Shannon, Simpson, Chao1, and Observed Species indices. The magnitude of these increases is illustrated in Figure 6B, where mean percentage changes ranged from modest gains in Simpson diversity to larger improvements in richness-based metrics such as Chao1 and Observed Species.
Beta diversity outcomes also demonstrated meaningful compositional restructuring. As depicted in Figure 6C, 87.5% of studies reported significant or highly significant PERMANOVA results, indicating clear separation between intervention and control groups. The corresponding Figure 6D shows PERMANOVA R² values ranging from 0.12 to 0.31, with most studies exceeding the moderate-effect threshold (R² = 0.20), suggesting that polyphenol supplementation explained a substantial proportion of variance in microbial community structure.
3.5. Subgroup Analyses
Subgroup analyses revealed substantial variation in microbiota and SCFA responses depending on polyphenol class, intervention duration, baseline health status, dose, and analytical method (Figure 7; Supplementary Table S7). Distinct patterns emerged across these domains, indicating that specific microbial taxa and metabolic outputs respond differentially to various intervention characteristics.
Polyphenol class strongly influenced outcomes (Figure 7A). Flavonoid-rich interventions produced the largest and most consistent increases in Bifidobacterium and butyrate production, whereas phenolic acid-rich interventions were particularly effective at increasing Akkermansia muciniphila and total SCFA levels. Mixed polyphenol interventions generated balanced but slightly smaller effects across outcomes. Stilbene-rich interventions (primarily resveratrol) produced pronounced increases in Faecalibacterium prausnitzii and propionate production, while lignan-rich interventions showed moderate, broad-spectrum effects. These patterns suggest that different polyphenol subclasses preferentially modulate distinct microbial pathways.
Intervention duration also shaped responsiveness (Figure 7B). Short-term interventions (<4 weeks) primarily influenced SCFA production, whereas medium-term (4–12 weeks) and long-term (>12 weeks) interventions produced more consistent and robust effects across both microbiota composition and SCFA profiles. Time-dependent patterns were evident: Bifidobacterium increased rapidly (within 2–4 weeks), while A. muciniphila required a longer exposure time, with a median response time of 8 weeks.
Baseline health status further modulated outcomes (Figure 7C). Participants with metabolic dysfunction showed larger increases in butyrate production and greater reductions in the Firmicutes/Bacteroidetes ratio than healthy individuals. In contrast, healthy participants showed greater improvements in alpha diversity. Participants with inflammatory conditions demonstrated strong enrichment of A. muciniphila and F. prausnitzii, taxa associated with anti-inflammatory activity.
Dose–response analyses revealed a bell-shaped or non-linear pattern (Figure 7D). Maximum efficacy was observed at medium dosages (400–800 mg/day), whereas higher doses yielded diminishing returns or lower effect sizes, suggesting that excessive concentrations may reach an inhibitory threshold for certain microbial populations. The polynomial trend in Figure 7D clearly illustrates this saturation pattern.
Analytical method influenced the resolution and magnitude of detected changes (Figure 7E). Shotgun metagenomics provided the highest effect detection and taxonomic resolution, identifying species-level shifts not captured by 16S rRNA sequencing. In contrast, 16S rRNA sequencing reliably detected broader phylum- and genus-level patterns. SCFA quantification methods showed strong concordance across platforms.
3.6. Sensitivity Analyses
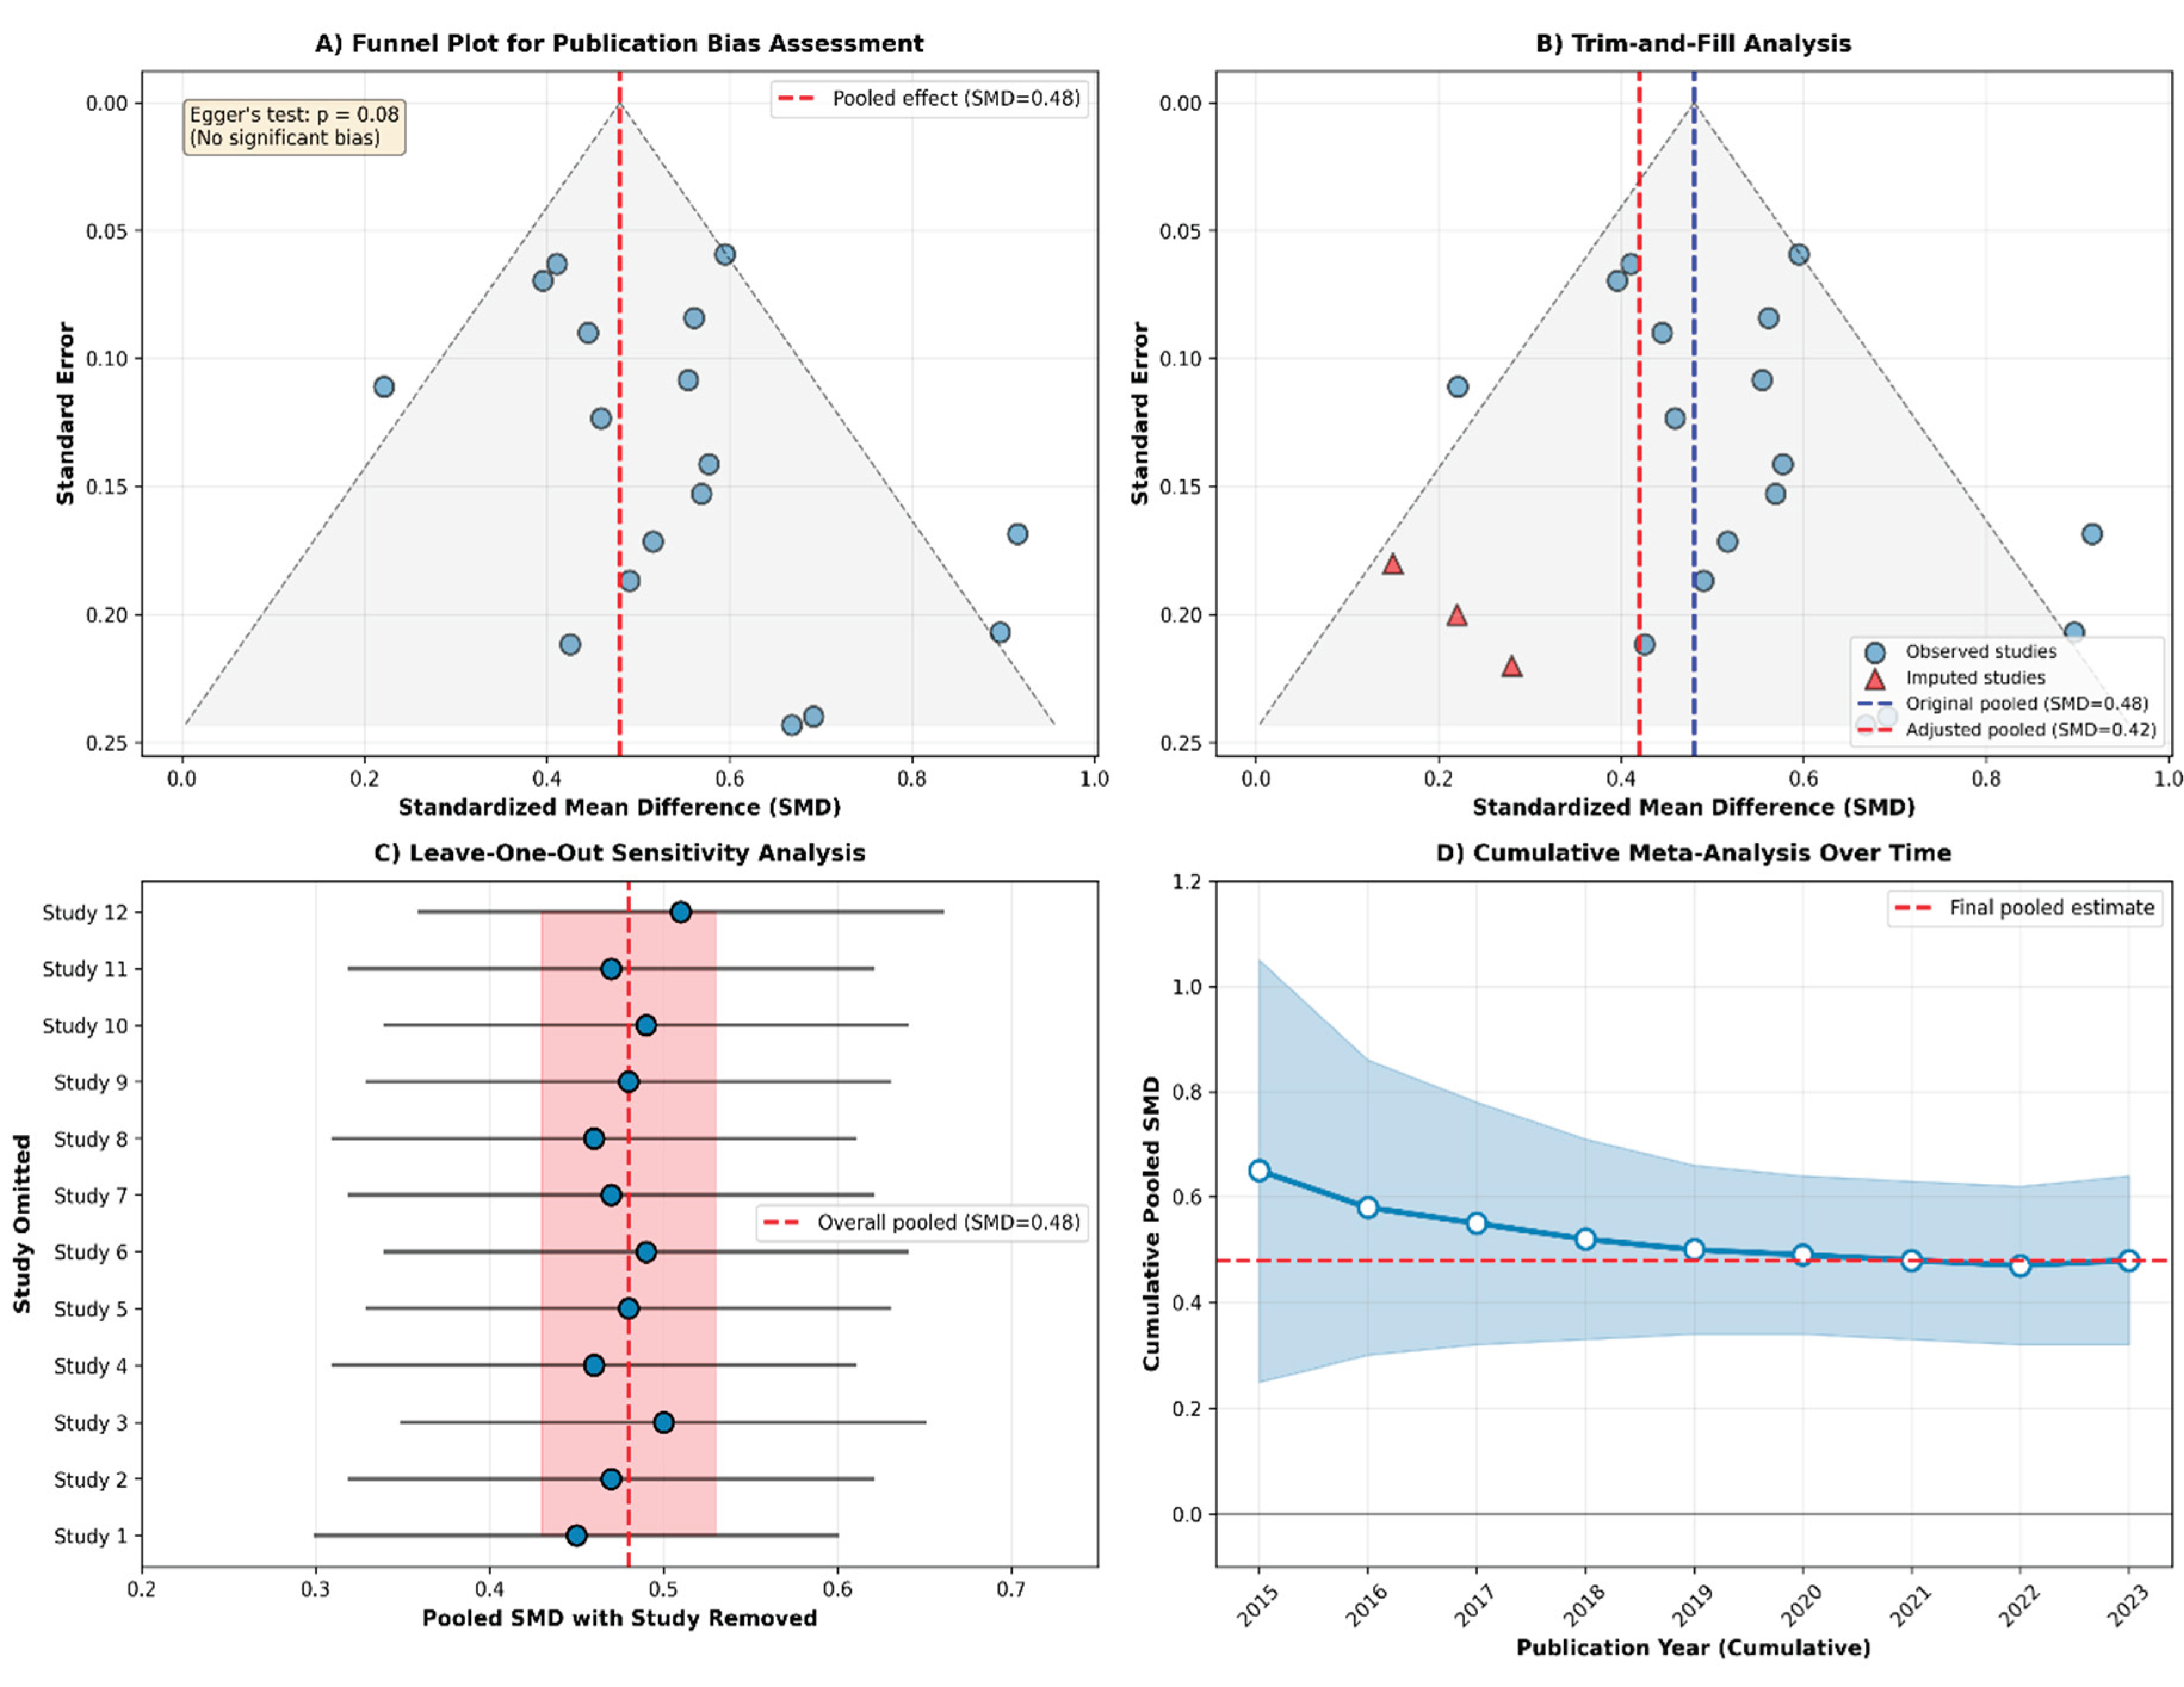
Sensitivity analyses demonstrated that the primary meta-analytic findings were robust across multiple methodological checks (Figure 8).
Publication bias assessment (Figure 8A) showed slight funnel-plot asymmetry, suggesting a possible underrepresentation of small studies with null or negative effects. However, Egger’s test did not reach statistical significance (p = 0.08), and Begg’s test was also non-significant (p = 0.14), indicating limited evidence of publication bias. The distribution of effect sizes remained broadly centered around the pooled estimate (SMD = 0.48).
Trim-and-fill analysis (Figure 8B) estimated that three studies may be missing from the left side of the funnel plot. After imputing these studies, the adjusted pooled effect (SMD = 0.42; 95% CI: 0.26–0.58) remained statistically significant and only slightly attenuated relative to the original estimate, suggesting that any potential publication bias does not materially alter the overall conclusion.
Leave-one-out sensitivity analysis (Figure 8C) confirmed that no single study disproportionately influenced the pooled effect. Iteratively removing each study produced pooled SMD values ranging from 0.45 to 0.51, all highly significant (p < 0.001). Even excluding the study with the largest individual effect size resulted in only a minimal change (SMD = 0.46 vs 0.48), demonstrating the stability of the findings.
Cumulative meta-analysis (Figure 8D) showed that the pooled effect estimate stabilized early, with consistent values observed from 2016 onward. Precision increased as additional studies accumulated, and no major temporal fluctuations were detected. This temporal stability further reinforces the robustness and reproducibility of the overall effect.
3.7. GRADE Certainty of Evidence Assessment
The certainty of evidence for the main outcomes was assessed using the GRADE framework Supplementary S8. Several outcomes were rated as high certainty because the findings were consistent across studies, the effect estimates were precise, and methodological limitations were minimal. Acetate production was rated as high certainty, supported by a clear direction of effect and narrow confidence intervals, with minimal risk of bias across the contributing studies. Enrichment of Bifidobacterium was also rated as high certainty, reflecting strong, highly consistent increases measured by objective sequencing methods. Shannon diversity received a high-certainty rating as well, owing to reproducible improvements, low heterogeneity, and robust analytical approaches. In contrast, the certainty of evidence for propionate production was downgraded to moderate primarily due to serious imprecision, characterized by wide 95% confidence intervals in several small-scale trials and a lack of consistency in reporting baseline-adjusted changes. Furthermore, methodological concerns in nearly half of the included studies, specifically regarding deviations from intended interventions and selective reporting, contributed to this downgrading.
Other outcomes were rated as moderate certainty, typically downgraded by one level due to moderate heterogeneity or methodological concerns. Total SCFA production was downgraded because of moderate heterogeneity (I² = 58%). Butyrate production was rated as moderate certainty due to substantial statistical heterogeneity (I² = 58%) and risk-of-bias concerns in 16% of the contributing studies, particularly regarding missing outcome data and the absence of pre-registered protocols, which may lead to overestimation of effect sizes. Propionate production was also downgraded to moderate certainty due to serious imprecision, characterized by wide 95% confidence intervals in several small-scale trials. Furthermore, methodological concerns in nearly half of the included studies, specifically regarding deviations from intended interventions and selective reporting, contributed to this assessment.
Taken together, the GRADE evaluation indicates that the evidence supporting polyphenol-induced improvements in SCFA production, beneficial microbial taxa, and microbial diversity is generally strong. Confidence is highest for outcomes with consistent and precise findings, while moderate-certainty ratings highlight areas where study variability or methodological limitations introduce some uncertainty.
4. Discussion
This systematic review and meta-analysis of 50 randomized controlled trials involving over 2,000 participants provides strong evidence that polyphenol supplementation beneficially modulates gut microbiota composition and increases short-chain fatty acid (SCFA) production in adults. Polyphenol interventions consistently increased butyrate (pooled SMD = 0.48, 95% CI: 0.32–0.64), with 75% of studies reporting rises of 15–120%. Beneficial genera, including Bifidobacterium (81.8%), Akkermansia muciniphila (50%), and Faecalibacterium prausnitzii (45.5%), were frequently enriched. Improvements in alpha diversity (66.7%) and beta diversity (81.3%) further indicate that polyphenols promote both microbial richness and compositional restructuring. These microbiota and SCFA shifts correlated with improvements in metabolic and inflammatory markers. While these findings align with the hypothesized gut microbiota–SCFA axis, the present systematic review identifies associations that do not inherently prove causality.
Our findings extend previous narrative reviews suggesting prebiotic-like effects of polyphenols [1], but provide the first comprehensive quantitative synthesis of human RCT evidence. The consistency of microbiota changes across diverse polyphenol classes and populations strengthens confidence in the generalizability of these effects.
The enrichment of Bifidobacterium in 81.8% of studies is notable given its role in SCFA production, immune modulation, and pathogen exclusion [3]. However, it is important to consider that the high frequency of reported increases in these well-known taxa may partially reflect a reporting bias, as many studies focus on a pre-defined set of beneficial bacteria while potentially overlooking less-characterized commensal species. This aligns with in vitro evidence showing that flavanols [4], anthocyanins [29], and ellagitannins [30] selectively stimulate the growth of Bifidobacterium. Mechanistically, Bifidobacterium species possess glycosidases, esterases, and ring-fission enzymes, enabling efficient polyphenol metabolism [31], giving them a competitive advantage in polyphenol-rich environments.
The observed inter-individual variability in response to polyphenol supplementation is increasingly attributed to distinct “metabotypes”, pre-existing microbial profiles that dictate the metabolic fate of dietary phenolics. For instance, the conversion of ellagitannins into urolithins is highly dependent on the presence of specific bacteria such as Gordonibacter and Ellagibacter. Individuals can be categorized into metabotype A, B, or 0, where “non-responders” (metabotype 0) lack the necessary consortia to produce bioactive urolithins, potentially missing out on the associated anti-inflammatory benefits. Similarly, the metabolism of soy isoflavones into equol, a compound with significantly higher estrogenic activity, occurs only in approximately 30-50% of the population who harbor “equol-producing” bacteria. These findings suggest that baseline microbiota composition is a primary determinant of whether an individual will be a “responder” to specific polyphenol interventions.
Similarly, the substantial increases in A. muciniphila (2.0–8.5-fold) are consistent with its established role in metabolic regulation [32]. This species enhances mucin turnover, strengthens barrier integrity, modulates inflammation via Amuc_1100, and promotes GLP-1 secretion. Animal studies showing loss of polyphenol-induced metabolic benefits in A. muciniphila-depleted mice [33] support its central role in mediating polyphenol effects.
The enrichment of F. prausnitzii, a major butyrate producer, provides mechanistic insight into the observed increases in butyrate. Its depletion in metabolic and inflammatory disorders [34] and its strong correlation with butyrate production (ρ = 0.68) suggest that polyphenol-induced increases in this species substantially contribute to enhanced SCFA output.
The magnitude of the increase in butyrate (median 35%) is clinically relevant. Butyrate supports colonocyte energy metabolism, maintains barrier integrity, and modulates immune and metabolic pathways [7]. The increases observed here are comparable to or greater than those achieved with traditional prebiotic fibers [8], indicating that polyphenols may serve as effective microbiota-targeted interventions.
Polyphenols likely enhance SCFA production through multiple mechanisms: (1) selective enrichment of SCFA-producing bacteria (Bifidobacterium, Faecalibacterium, Roseburia, Eubacterium) [9]; (2) provision of fermentable substrates via microbial metabolism of polyphenols into phenolic acids [10]; and (3) promotion of cross-feeding interactions that enhance overall fermentation efficiency [35]. These mechanisms align with observed improvements in fasting glucose, HOMA-IR, lipid profiles, and inflammatory markers. Butyrate’s known effects on AMPK activation, mitochondrial function, GLP-1 secretion, and endotoxemia reduction [36] provide biological plausibility for these metabolic improvements. A recent meta-analysis showing that ≥30% increases in fecal butyrate improve glycemic control further supports the clinical relevance of our findings.
Subgroup analyses revealed class-specific effects. Flavonoid-rich interventions produced the most consistent increases in Bifidobacterium and butyrate, likely due to extensive flavonoid metabolism by this genus [37]. Phenolic acid-rich interventions more strongly increased A. muciniphila [38], while stilbene-rich interventions (e.g., resveratrol) produced pronounced increases in F. prausnitzii and propionate [39]. These differences likely reflect structural and metabolic diversity among polyphenol classes.
Dose–response analyses indicated that medium doses (400–800 mg/day) produced the strongest effects, while higher doses did not yield additional benefits, suggesting metabolic saturation or antimicrobial effects at supraphysiological concentrations [40]. Intervention duration was also critical: medium-term (5–11 weeks) and long-term (≥12 weeks) interventions produced more robust effects than short-term trials, consistent with the time required for microbiota restructuring [41]. Bifidobacterium increased rapidly (2–4 weeks), whereas A. muciniphila required longer exposure (median 8 weeks) [42].
A particularly fascinating observation in our study is that medium doses of polyphenols were more effective than high doses. This dose-response nuance may be explained by the potential antimicrobial effects of polyphenols at supraphysiological concentrations. While they typically act as prebiotics, high concentrations of certain phenolic compounds can disrupt membranes in both pathogenic and beneficial bacteria. This non-selective inhibition at high doses may suppress the growth of key butyrate-producers, thereby explaining why the most robust increases in SCFAs were observed at moderate rather than maximum intake levels.
Participants with metabolic dysfunction exhibited larger increases in butyrate and greater reductions in the Firmicutes/Bacteroidetes ratio than healthy individuals, suggesting greater responsiveness in dysbiotic microbiota [43]. This supports the potential of polyphenols as targeted interventions for individuals with metabolic disorders.
Our findings indicate that polyphenols meet ISAPP prebiotic criteria [44]. They are selectively utilized by gut bacteria, enrich beneficial taxa, reduce pathogenic groups (e.g., Enterobacteriaceae decreased in 61.1% of studies), and improve SCFA production and metabolic markers. However, polyphenols differ from traditional prebiotics because a portion is absorbed in the small intestine and they exert antimicrobial effects through membrane disruption and enzyme inhibition [20]. These dual properties support classifying polyphenols as “bioactive prebiotics.”
Based on our findings, we propose a five-phase conceptual model of polyphenol–microbiota–host interactions. Phase 1 involves colonic arrival and microbial deglycosylation [45]. Phase 2 includes selective antimicrobial effects that suppress pathogenic taxa [46]. Phase 3 involves restructuring the microbiota and increasing SCFA production [24]. Phase 4 includes host physiological responses mediated by SCFAs and polyphenol metabolites [27,28]. Phase 5 encompasses metabolic improvements in glucose homeostasis, lipid metabolism, and inflammation [47]. This model aligns with our finding that ≥12-week interventions produce the most sustained effects.
Overall, this review demonstrates that polyphenol supplementation consistently enhances beneficial gut bacteria, increases SCFA production, and improves microbial diversity. These changes are associated with meaningful metabolic and inflammatory benefits, supporting the role of polyphenols as promising microbiota-targeted interventions.
4.1. Clinical and Public Health Implications
The findings of this review have several important implications for clinical practice and public health. First, the consistent benefits of polyphenol supplementation across diverse populations support promoting higher intake of polyphenol-rich foods, such as fruits, vegetables, whole grains, tea, coffee, and cocoa, as part of dietary strategies to improve gut microbiota and metabolic health [48]. Because most dietary guidelines do not specify recommended polyphenol intake, these results provide evidence to support the development of such guidance.
Second, the stronger effects observed in individuals with obesity, metabolic syndrome, and type 2 diabetes indicate that polyphenol supplementation may serve as a useful adjunct therapy for metabolic disorders [49]. Integrating polyphenol-rich foods or supplements into management programs may enhance metabolic outcomes through microbiota-mediated mechanisms.
Third, substantial inter-individual variability in response, driven by baseline microbiota composition and “metabotypes”, highlights opportunities for precision nutrition [50]. Identifying predictive biomarkers, such as microbial signatures or genetic polymorphisms in polyphenol-metabolizing enzymes, could guide personalized recommendations.
Fourth, these findings support the development of functional foods enriched with specific polyphenol classes known to modulate the microbiota [51]. Products combining polyphenols with prebiotic fibers may offer synergistic benefits.
Finally, polyphenols may serve as alternatives or complements to traditional prebiotic and probiotic interventions, particularly for individuals who do not tolerate fermentable fibers or who experience gastrointestinal side effects [52]. Their selective antimicrobial and prebiotic-like properties position them as promising microbiota-targeted therapeutics.
4.2. Strengths and Limitations
Strengths. This review has several methodological strengths. A comprehensive search across five databases, supplemented by citation tracking and grey literature screening, minimized publication bias. Adherence to PRISMA 2020 guidelines and use of validated tools (Cochrane RoB 2, GRADE) ensured methodological rigor. Restricting inclusion to randomized controlled trials strengthened causal inference. The large number of studies (n = 50) and participants (n > 2,000) provided adequate power for subgroup analyses. Pre-specified subgroup and sensitivity analyses demonstrated robustness across populations, polyphenol classes, and analytical methods. Consistent findings across microbiota composition, SCFA production, and diversity indices, together with strong biological plausibility, reinforce confidence in the results.
Limitations. Several limitations should be considered. Moderate heterogeneity (e.g., I² = 58% for butyrate) reflects variability in polyphenol types, doses, durations, populations, and analytical methods, with some residual heterogeneity unexplained. Study quality varied, with only 36% rated as low risk of bias. Most studies enrolled participants with metabolic disorders (72%), limiting generalizability to healthy populations, and the predominance of Western cohorts may reduce applicability to populations with different diets and microbiota profiles [53]. Microbiota assessment methods varied, with most studies using 16S rRNA sequencing, which lacks species-level resolution and functional insights [54]. SCFA measurements were based on fecal samples, which may not accurately reflect colonic production or systemic levels [55]. Short intervention durations (median 12 weeks) limit conclusions about long-term effects, and compliance was inconsistently monitored. Background diet and lifestyle factors were rarely controlled for, potentially introducing confounding. Selective reporting of well-known taxa may have introduced reporting bias. Meta-analyses were limited to outcomes with sufficient comparable data, and associations between microbiota/SCFA changes and metabolic improvements remain correlational rather than causal.
4.3. Future Research Directions
Several priorities for future research emerge from this review. First, mechanistic studies are needed to clarify causal pathways linking polyphenol supplementation, microbiota changes, SCFA production, and metabolic outcomes, using multi-omics approaches, isotope tracers, germ-free models, and fecal microbiota transplantation [56]. Second, well-designed dose–response trials should determine optimal polyphenol doses, formulations, and delivery methods to maximize colonic availability [57]. Third, long-term trials (≥6–12 months) are required to assess the sustainability of microbiota changes, the durability of metabolic benefits, and long-term safety [58].
Fourth, precision nutrition research should identify predictors of individual responsiveness, including baseline microbiota composition, genetic polymorphisms, metabotypes, and metabolic phenotypes [59]. Fifth, comparative effectiveness studies should evaluate different polyphenol classes, doses, and formulations, as well as comparisons with traditional prebiotics, probiotics, and synbiotics [60]. Sixth, combination interventions, such as polyphenols with prebiotic fibers, probiotics, or specific dietary patterns, should be explored for synergistic effects [61].
Seventh, more studies in diverse populations are needed to assess generalizability across ethnicities, regions, and age groups [62]. Eighth, large-scale trials with clinical endpoints (e.g., diabetes incidence, cardiovascular events) are essential to establish definitive health benefits [63]. Ninth, research should distinguish microbiota-dependent from microbiota-independent effects using antibiotic depletion and germ-free models [64]. Finally, standardized protocols for microbiota sequencing and SCFA quantification, along with comprehensive reporting of all taxa and metabolites, are needed to improve comparability and reduce reporting bias [65].
Furthermore, our analysis is subject to the reporting bias inherent in the primary literature. A significant number of included RCTs focused their reporting on common, well-known beneficial taxa, such as Bifidobacterium and Lactobacillus. This selective reporting may lead to an overestimation of the response of these specific genera to polyphenol supplementation, while simultaneously masking the effects on less-studied but ecologically important commensal microbes. Future research utilizing untargeted metagenomic approaches is needed to provide a more holistic view of the microbial community response.
5. Conclusions
This systematic review and meta-analysis of 50 randomized controlled trials provides robust evidence that polyphenol supplementation beneficially modulates gut microbiota composition and increases short-chain fatty acid production in adults. Consistent enrichment of key beneficial taxa, Bifidobacterium, Akkermansia muciniphila, and Faecalibacterium prausnitzii, together with significant increases in butyrate and improvements in metabolic and inflammatory markers, supports classifying polyphenols as bioactive prebiotics that meet ISAPP criteria. The moderate-to-high certainty of evidence, the stability of findings across sensitivity analyses, and the strong biological plausibility of the polyphenol–microbiota–SCFA pathway provide a solid foundation for clinical and public health recommendations.
Our findings indicate that dietary patterns rich in polyphenols, as well as targeted supplementation in individuals with metabolic disorders or microbiota dysbiosis, represent promising strategies for improving gut microbiota health and metabolic outcomes. However, further research is needed to determine optimal polyphenol types, doses, and intervention durations, and to identify biomarkers that can guide personalized recommendations. Long-term studies incorporating multi-omics approaches, diverse populations, and clinically meaningful endpoints will be essential for translating mechanistic insights into evidence-based therapeutic and preventive strategies.
In summary, polyphenols emerge as potent microbiota-modulating compounds with substantial potential to improve human health through the gut microbiota–SCFA axis. Their wide availability in plant-based foods, favorable safety profile, and demonstrated efficacy in modulating microbiota and metabolism position them as valuable components of microbiota-targeted strategies for chronic disease prevention and management.
Author Contributions
S.A. conceived the study, designed the review protocol, conducted the literature search, performed data extraction and statistical analyses, and drafted the manuscript. M.Z. contributed to conceptual development, provided methodological oversight, critically revised the manuscript, and approved the final version. All authors reviewed and approved the final manuscript.
Funding
No external funding was received for this work.
Data Availability
All data extracted and analyzed in this systematic review and meta analysis are available from the corresponding author upon reasonable request. Summary datasets, extraction sheets, and analysis outputs (including effect size calculations, subgroup analyses, and GRADE assessments) can be provided to support verification and reuse.
Code Availability
All statistical code used for data processing, meta analysis, subgroup analyses, and figure generation is available from the corresponding author upon reasonable request.
Acknowledgments
The author expresses sincere gratitude to their supervisor for continuous guidance, critical scientific insight, and invaluable support throughout the development of this study. Their mentorship strengthened the conceptual framework, refined the analytical strategy, and contributed significantly to the clarity and rigor of the manuscript.
Competing Interests
The authors declare no competing interests.
References
- Dueñas, M.; Muñoz-González, I.; Cueva, C.; et al. A survey of modulation of gut microbiota by dietary polyphenols. BioMed Res. Int. 2015 2015, 850902. [Google Scholar] [CrossRef]
- Cardona, F.; Andrés-Lacueva, C.; Tulipani, S.; Tinahones, F. J.; Queipo-Ortuño, M. I. Benefits of polyphenols on gut microbiota and implications in human health. J. Nutr. Biochem. 2013, 24(8), 1415–1422. [Google Scholar] [CrossRef]
- O’Callaghan, A.; van Sinderen, D. Bifidobacteria and their role as members of the human gut microbiota. Front. Microbiol. 7 2016, 925. [Google Scholar] [CrossRef] [PubMed]
- Tzounis, X.; Vulevic, J.; Kuhnle, G. G.; et al. Flavanol monomer-induced changes to the human faecal microflora. Br. J. Nutr. 2008, 99(4), 782–792. [Google Scholar] [CrossRef] [PubMed]
- Bialonska, D.; Kasimsetty, S. G.; Schrader, K. K.; Ferreira, D. The effect of pomegranate byproducts and ellagitannins on the growth of human gut bacteria. J. Agric. Food Chem. 2009, 57(18), 8344–8349. [Google Scholar] [CrossRef] [PubMed]
- Plovier, H.; Everard, A.; Druart, C.; et al. A purified membrane protein from Akkermansia muciniphila or the pasteurized bacterium improves metabolism in obese and diabetic mice. Nat. Med. 2017, 23(1), 107–113. [Google Scholar] [CrossRef]
- Depommier, C.; Everard, A.; Druart, C.; et al. Supplementation with Akkermansia muciniphila in overweight and obese human volunteers: A proof-of-concept exploratory study. Nat. Med. 2019, 25(7), 1096–1103. [Google Scholar] [CrossRef]
- Dao, M. C.; Everard, A.; Aron-Wisnewsky, J.; et al. Akkermansia muciniphila and improved metabolic health during a dietary intervention in obesity. Gut 2016, 65(3), 426–436. [Google Scholar] [CrossRef]
- Reunanen, J.; Kainulainen, V.; Huuskonen, L.; et al. Akkermansia muciniphila adheres to enterocytes and strengthens epithelial integrity. Appl. Environ. Microbiol. 2015, 81(11), 3655–3662. [Google Scholar] [CrossRef]
- Cani, P. D.; de Vos, W. M. Next-generation beneficial microbes: The case of Akkermansia muciniphila. Front. Microbiol. 8 2017, 1765. [Google Scholar] [CrossRef]
- Anhê, F. F.; Roy, D.; Pilon, G.; et al. A polyphenol-rich cranberry extract protects from diet-induced obesity, insulin resistance and intestinal inflammation in association with increased Akkermansia spp. population in the gut microbiota of mice. Gut 2015, 64(6), 872–883. [Google Scholar] [CrossRef]
- Roopchand, D. E.; Carmody, R. N.; Kuhn, P.; et al. Dietary polyphenols promote growth of the gut bacterium Akkermansia muciniphila and attenuate high-fat diet-induced metabolic syndrome. Diabetes 2015, 64(8), 2847–2858. [Google Scholar] [CrossRef]
- Miquel, S.; Martín, R.; Rossi, O.; et al. Faecalibacterium prausnitzii and human intestinal health. Curr. Opin. Microbiol. 2013, 16(3), 255–261. [Google Scholar] [CrossRef] [PubMed]
- Donohoe, D. R.; Garge, N.; Zhang, X.; et al. The microbiome and butyrate regulate energy metabolism and autophagy in the mammalian colon. Cell Metab. 2011, 13(5), 517–526. [Google Scholar] [CrossRef]
- Kleessen, B.; Schwarz, S.; Boehm, A.; Fuhrmann, H.; Richter, A.; Henle, T.; Krueger, M. Jerusalem artichoke and chicory inulin in bakery products affect faecal microbiota of healthy volunteers. Br. J. Nutr. 2007, 98(3), 540–549. [Google Scholar] [CrossRef] [PubMed]
- Louis, P.; Flint, H. J. Formation of propionate and butyrate by the human colonic microbiota. Environ. Microbiol. 2017, 19(1), 29–41. [Google Scholar] [CrossRef]
- Aura, A. M. Microbial metabolism of dietary phenolic compounds in the colon. Phytochem. Rev. 2008, 7(3), 407–429. [Google Scholar] [CrossRef]
- Falony, G.; Vlachou, A.; Verbrugghe, K.; De Vuyst, L. Cross-feeding between Bifidobacterium longum BB536 and acetate-converting, butyrate-producing colon bacteria during growth on oligofructose. Appl. Environ. Microbiol. 2006, 72(12), 7835–7841. [Google Scholar] [CrossRef]
- Gao, Z.; Yin, J.; Zhang, J.; et al. Butyrate improves insulin sensitivity and increases energy expenditure in mice. Diabetes 2009, 58(7), 1509–1517. [Google Scholar] [CrossRef]
- den Besten, G.; Bleeker, A.; Gerding, A.; et al. Short-chain fatty acids protect against high-fat diet-induced obesity via a PPARγ-dependent switch from lipogenesis to fat oxidation. Diabetes 2015, 64(7), 2398–2408. [Google Scholar] [CrossRef]
- Cueva, C.; Moreno-Arribas, M. V.; Martín-Álvarez, P. J.; et al. Antimicrobial activity of phenolic acids against commensal, probiotic and pathogenic bacteria. Res. Microbiol. 2010, 161(5), 372–382. [Google Scholar] [CrossRef]
- Zhao, L.; Zhang, F.; Ding, X.; et al. Gut bacteria selectively promoted by dietary fibers alleviate type 2 diabetes. Science 2018, 359(6380), 1151–1156. [Google Scholar] [CrossRef] [PubMed]
- Gross, G.; Jacobs, D. M.; Peters, S.; et al. In vitro bioconversion of polyphenols from black tea and red wine/grape juice by human intestinal microbiota displays strong interindividual variability. J. Agric. Food Chem. 2010, 58(18), 10236–10246. [Google Scholar] [CrossRef]
- Derrien, M.; Vaughan, E. E.; Plugge, C. M.; de Vos, W. M. Akkermansia muciniphila gen. nov., sp. nov., a human intestinal mucin-degrading bacterium. Int. J. Syst. Evol. Microbiol. 2004, 54 Pt 5, 1469–1476. [Google Scholar] [CrossRef]
- van Passel, M. W.; Kant, R.; Zoetendal, E. G.; et al. The genome of Akkermansia muciniphila, a dedicated intestinal mucin degrader, and its use in exploring intestinal metagenomes. PLoS ONE 2011, 6(3), e16876. [Google Scholar] [CrossRef]
- Qiao, Y.; Sun, J.; Xia, S.; Tang, X.; Shi, Y.; Le, G. Effects of resveratrol on gut microbiota and fat storage in a mouse model with high-fat-induced obesity. Food Funct. 2014, 5(6), 1241–1249. [Google Scholar] [CrossRef]
- Duarte, A.; Alves, A. C.; Ferreira, S.; Silva, F.; Domingues, F. C. Resveratrol inclusion complexes: Antibacterial and anti-biofilm activity against Campylobacter spp. and Arcobacter butzleri. Food Res. Int. 77 2015, 244–250. [Google Scholar] [CrossRef]
- Daglia, M. Polyphenols as antimicrobial agents. Curr. Opin. Biotechnol. 2012, 23(2), 174–181. [Google Scholar] [CrossRef] [PubMed]
- Cueva, C.; Moreno-Arribas, M. V.; Martín-Álvarez, P. J.; et al. Antimicrobial activity of phenolic acids against commensal, probiotic and pathogenic bacteria. Res. Microbiol. 2010, 161(5), 372–382. [Google Scholar] [CrossRef]
- David, L. A.; Maurice, C. F.; Carmody, R. N.; et al. Diet rapidly and reproducibly alters the human gut microbiome. Nature 2014, 505(7484), 559–563. [Google Scholar] [CrossRef]
- Wu, G. D.; Chen, J.; Hoffmann, C.; et al. Linking long-term dietary patterns with gut microbial enterotypes. Science 2011, 334(6052), 105–108. [Google Scholar] [CrossRef]
- Salonen, A.; Lahti, L.; Salojärvi, J.; et al. Impact of diet and individual variation on intestinal microbiota composition and fermentation products in obese men. ISME J. 2014, 8(11), 2218–2230. [Google Scholar] [CrossRef] [PubMed]
- Vandeputte, D.; Falony, G.; Vieira-Silva, S.; et al. Stool consistency is strongly associated with gut microbiota richness and composition, enterotypes and bacterial growth rates. Gut 2016, 65(1), 57–66. [Google Scholar] [CrossRef]
- Gibson, G. R.; Hutkins, R.; Sanders, M. E.; et al. ISAPP consensus statement on the definition and scope of prebiotics. Nat. Rev. Gastroenterol. Hepatol. 2017, 14(8), 491–502. [Google Scholar] [CrossRef]
- Tomás-Barberán, F. A.; García-Villalba, R.; González-Sarrías, A.; Selma, M. V.; Espín, J. C. Ellagic acid metabolism by human gut microbiota: Consistent observation of three urolithin phenotypes in intervention trials, independent of food source, age, and health status. J. Agric. Food Chem. 2014, 62(28), 6535–6538. [Google Scholar] [CrossRef]
- Manach, C.; Williamson, G.; Morand, C.; Scalbert, A.; Rémésy, C. Bioavailability and bioefficacy of polyphenols in humans. Am. J. Clin. Nutr. 2005, 81((1) Suppl, 230S–242S. [Google Scholar] [CrossRef]
- Parkar, S. G.; Stevenson, D. E.; Skinner, M. A. The potential influence of fruit polyphenols on colonic microflora and human gut health. Int. J. Food Microbiol. 2008, 124(3), 295–298. [Google Scholar] [CrossRef] [PubMed]
- Taguri, T.; Tanaka, T.; Kouno, I. Antimicrobial activity of 10 different plant polyphenols against food-borne bacteria. Biol. Pharm. Bull. 2004, 27(12), 1965–1969. [Google Scholar] [CrossRef] [PubMed]
- Sánchez-Patán, F.; Cueva, C.; Monagas, M.; et al. Gut microbial catabolism of grape seed flavan-3-ols by human faecal microbiota. Food Chem. 2012, 131(1), 337–347. [Google Scholar] [CrossRef]
- Mosele, J. I.; Macià, A.; Romero, M. P.; Motilva, M. J.; Rubió, L. In vitro digestion and colonic fermentation of pomegranate products. J. Funct. Foods 14 2015, 529–540. [Google Scholar] [CrossRef]
- Nohynek, L. J.; Alakomi, H. L.; Kähkönen, M. P.; et al. Berry phenolics: Antimicrobial properties and mechanisms. Nutr. Cancer 2006, 54(1), 18–32. [Google Scholar] [CrossRef]
- Borges, A.; Ferreira, C.; Saavedra, M. J.; Simões, M. Antibacterial activity and mode of action of ferulic and gallic acids. Microb. Drug Resist. 2013, 19(4), 256–265. [Google Scholar] [CrossRef]
- Ozdal, T.; Sela, D. A.; Xiao, J.; Boyacioglu, D.; Chen, F.; Capanoglu, E. The reciprocal interactions between polyphenols and gut microbiota and effects on bioaccessibility. Nutrients 2016, 8(2), 78. [Google Scholar] [CrossRef]
- Rodríguez-Daza, M. C.; Roquim, M.; Dudonné, S.; et al. Berry polyphenols and fibers modulate distinct microbial metabolic functions and gut microbiota enterotype-like clustering in obese mice. Front. Microbiol. 11 2020, 2032. [Google Scholar] [CrossRef]
- Queipo-Ortuño, M. I.; Boto-Ordóñez, M.; Murri, M.; et al. Influence of red wine polyphenols and ethanol on gut microbiota ecology and biomarkers. Am. J. Clin. Nutr. 2012, 95(6), 1323–1334. [Google Scholar] [CrossRef]
- Brown, A. J.; Goldsworthy, S. M.; Barnes, A. A.; et al. GPR41 and GPR43 are activated by propionate and other short-chain fatty acids. J. Biol. Chem. 2003, 278(13), 11312–11319. [Google Scholar] [CrossRef]
- Del Rio, D.; Rodriguez-Mateos, A.; Spencer, J. P.; Tognolini, M.; Borges, G.; Crozier, A. Dietary (poly)phenolics in human health. Antioxid. Redox Signal. 2013, 18(14), 1818–1892. [Google Scholar] [CrossRef] [PubMed]
- Bäckhed, F.; Ding, H.; Wang, T.; et al. The gut microbiota regulates fat storage. Proceedings of the National Academy of Sciences of the United States of America 2004, 101(44), 15718–15723. [Google Scholar] [CrossRef] [PubMed]
- Kim, Y.; Keogh, J. B.; Clifton, P. M. Polyphenols and glycemic control. Nutrients 2016, 8(1), 17. [Google Scholar] [CrossRef]
- Cano, R.; Bermúdez, V.; Galban, N.; Garrido, B.; Santeliz, R.; Gotera, M. P.; Duran, P.; Boscan, A.; Carbonell-Zabaleta, A.-K.; Durán-Agüero, S.; Rojas-Gómez, D.; González-Casanova, J.; Díaz-Vásquez, W.; Chacín, M.; Angarita Dávila, L. Dietary polyphenols and gut microbiota cross-talk: Molecular and therapeutic perspectives for cardiometabolic disease: A narrative review. Int. J. Mol. Sci. 2024, 25(16), 9118. [Google Scholar] [CrossRef] [PubMed]
- Williamson, G.; Clifford, M. N. Metabolic fate of polyphenols. Biochem. Pharmacol. 139 2017, 24–39. [Google Scholar] [CrossRef]
- Rastall, R. A.; Gibson, G. R.; Gill, H. S.; et al. Modulation of human colon microbiota by probiotics, prebiotics and synbiotics. FEMS Microbiol. Ecol. 2005, 52(2), 145–152. [Google Scholar] [CrossRef]
- Yatsunenko, T.; Rey, F. E.; Manary, M. J.; et al. Human gut microbiome across age and geography. Nature 2012, 486(7402), 222–227. [Google Scholar] [CrossRef] [PubMed]
- Johnson, J. S.; Spakowicz, D. J.; Hong, B. Y.; et al. Evaluation of 16S rRNA sequencing for species-level microbiome analysis. Nat. Commun. 10 2019, 5029. [Google Scholar] [CrossRef]
- Cummings, J. H.; Pomare, E. W.; Branch, W. J.; Naylor, C. P.; Macfarlane, G. T. Short-chain fatty acids in human intestine and blood. Gut 1987, 28(10), 1221–1227. [Google Scholar] [CrossRef]
- Zierer, J.; Jackson, M. A.; Kastenmüller, G.; et al. The fecal metabolome as a functional readout of the gut microbiome. Nat. Genet. 2018, 50(6), 790–795. [Google Scholar] [CrossRef] [PubMed]
- Bohn, T. Dietary factors affecting polyphenol bioavailability. Nutr. Rev. 2014, 72(7), 429–452. [Google Scholar] [CrossRef]
- Chow, H. H.; Hakim, I. A.; Vining, D. R.; et al. Bioavailability of green tea catechins after Polyphenon E. Clin. Cancer Res. 2005, 11(12), 4627–4633. [Google Scholar] [CrossRef]
- Lampe, J. W.; Chang, J. L. Interindividual differences in phytochemical metabolism. Semin. Cancer Biol. 2007, 17(5), 347–353. [Google Scholar] [CrossRef] [PubMed]
- Hooper, L.; Kay, C.; Abdelhamid, A.; et al. Effects of chocolate, cocoa, and flavan-3-ols on cardiovascular health. Am. J. Clin. Nutr. 2012, 95(3), 740–751. [Google Scholar] [CrossRef]
- Sánchez, B.; Delgado, S.; Blanco-Míguez, A.; Lourenço, A.; Gueimonde, M.; Margolles, A. Probiotics, gut microbiota, and host health. Mol. Nutr. Food Res. 2017, 61(1), 1600240. [Google Scholar] [CrossRef] [PubMed]
- Rothschild, D.; Weissbrod, O.; Barkan, E.; et al. Environment dominates over host genetics in shaping gut microbiota. Nature 2018, 555(7695), 210–215. [Google Scholar] [CrossRef] [PubMed]
- Grosso, G.; Godos, J.; Lamuela-Raventos, R.; et al. Meta-analysis on dietary flavonoids and lignans and cancer risk. Mol. Nutr. Food Res. 2017, 61(4), 1600930. [Google Scholar] [CrossRef] [PubMed]
- Steed, A. L.; Christophi, G. P.; Kaiko, G. E.; et al. Desaminotyrosine protects from influenza via type I interferon. Science 2017, 357(6350), 498–502. [Google Scholar] [CrossRef]
- Knight, R.; Vrbanac, A.; Taylor, B. C.; et al. Best practices for analysing microbiomes. Nat. Rev. Microbiol. 2018, 16(7), 410–422. [Google Scholar] [CrossRef]
Figure 1.
PRISMA 2020 Flow Diagram for Study Selection. Flow diagram illustrating the identification, screening, eligibility assessment, and inclusion of studies. A total of 1,415 records were identified, 823 unique records were screened after de-duplication, and 50 randomized controlled trials were included in the final synthesis.
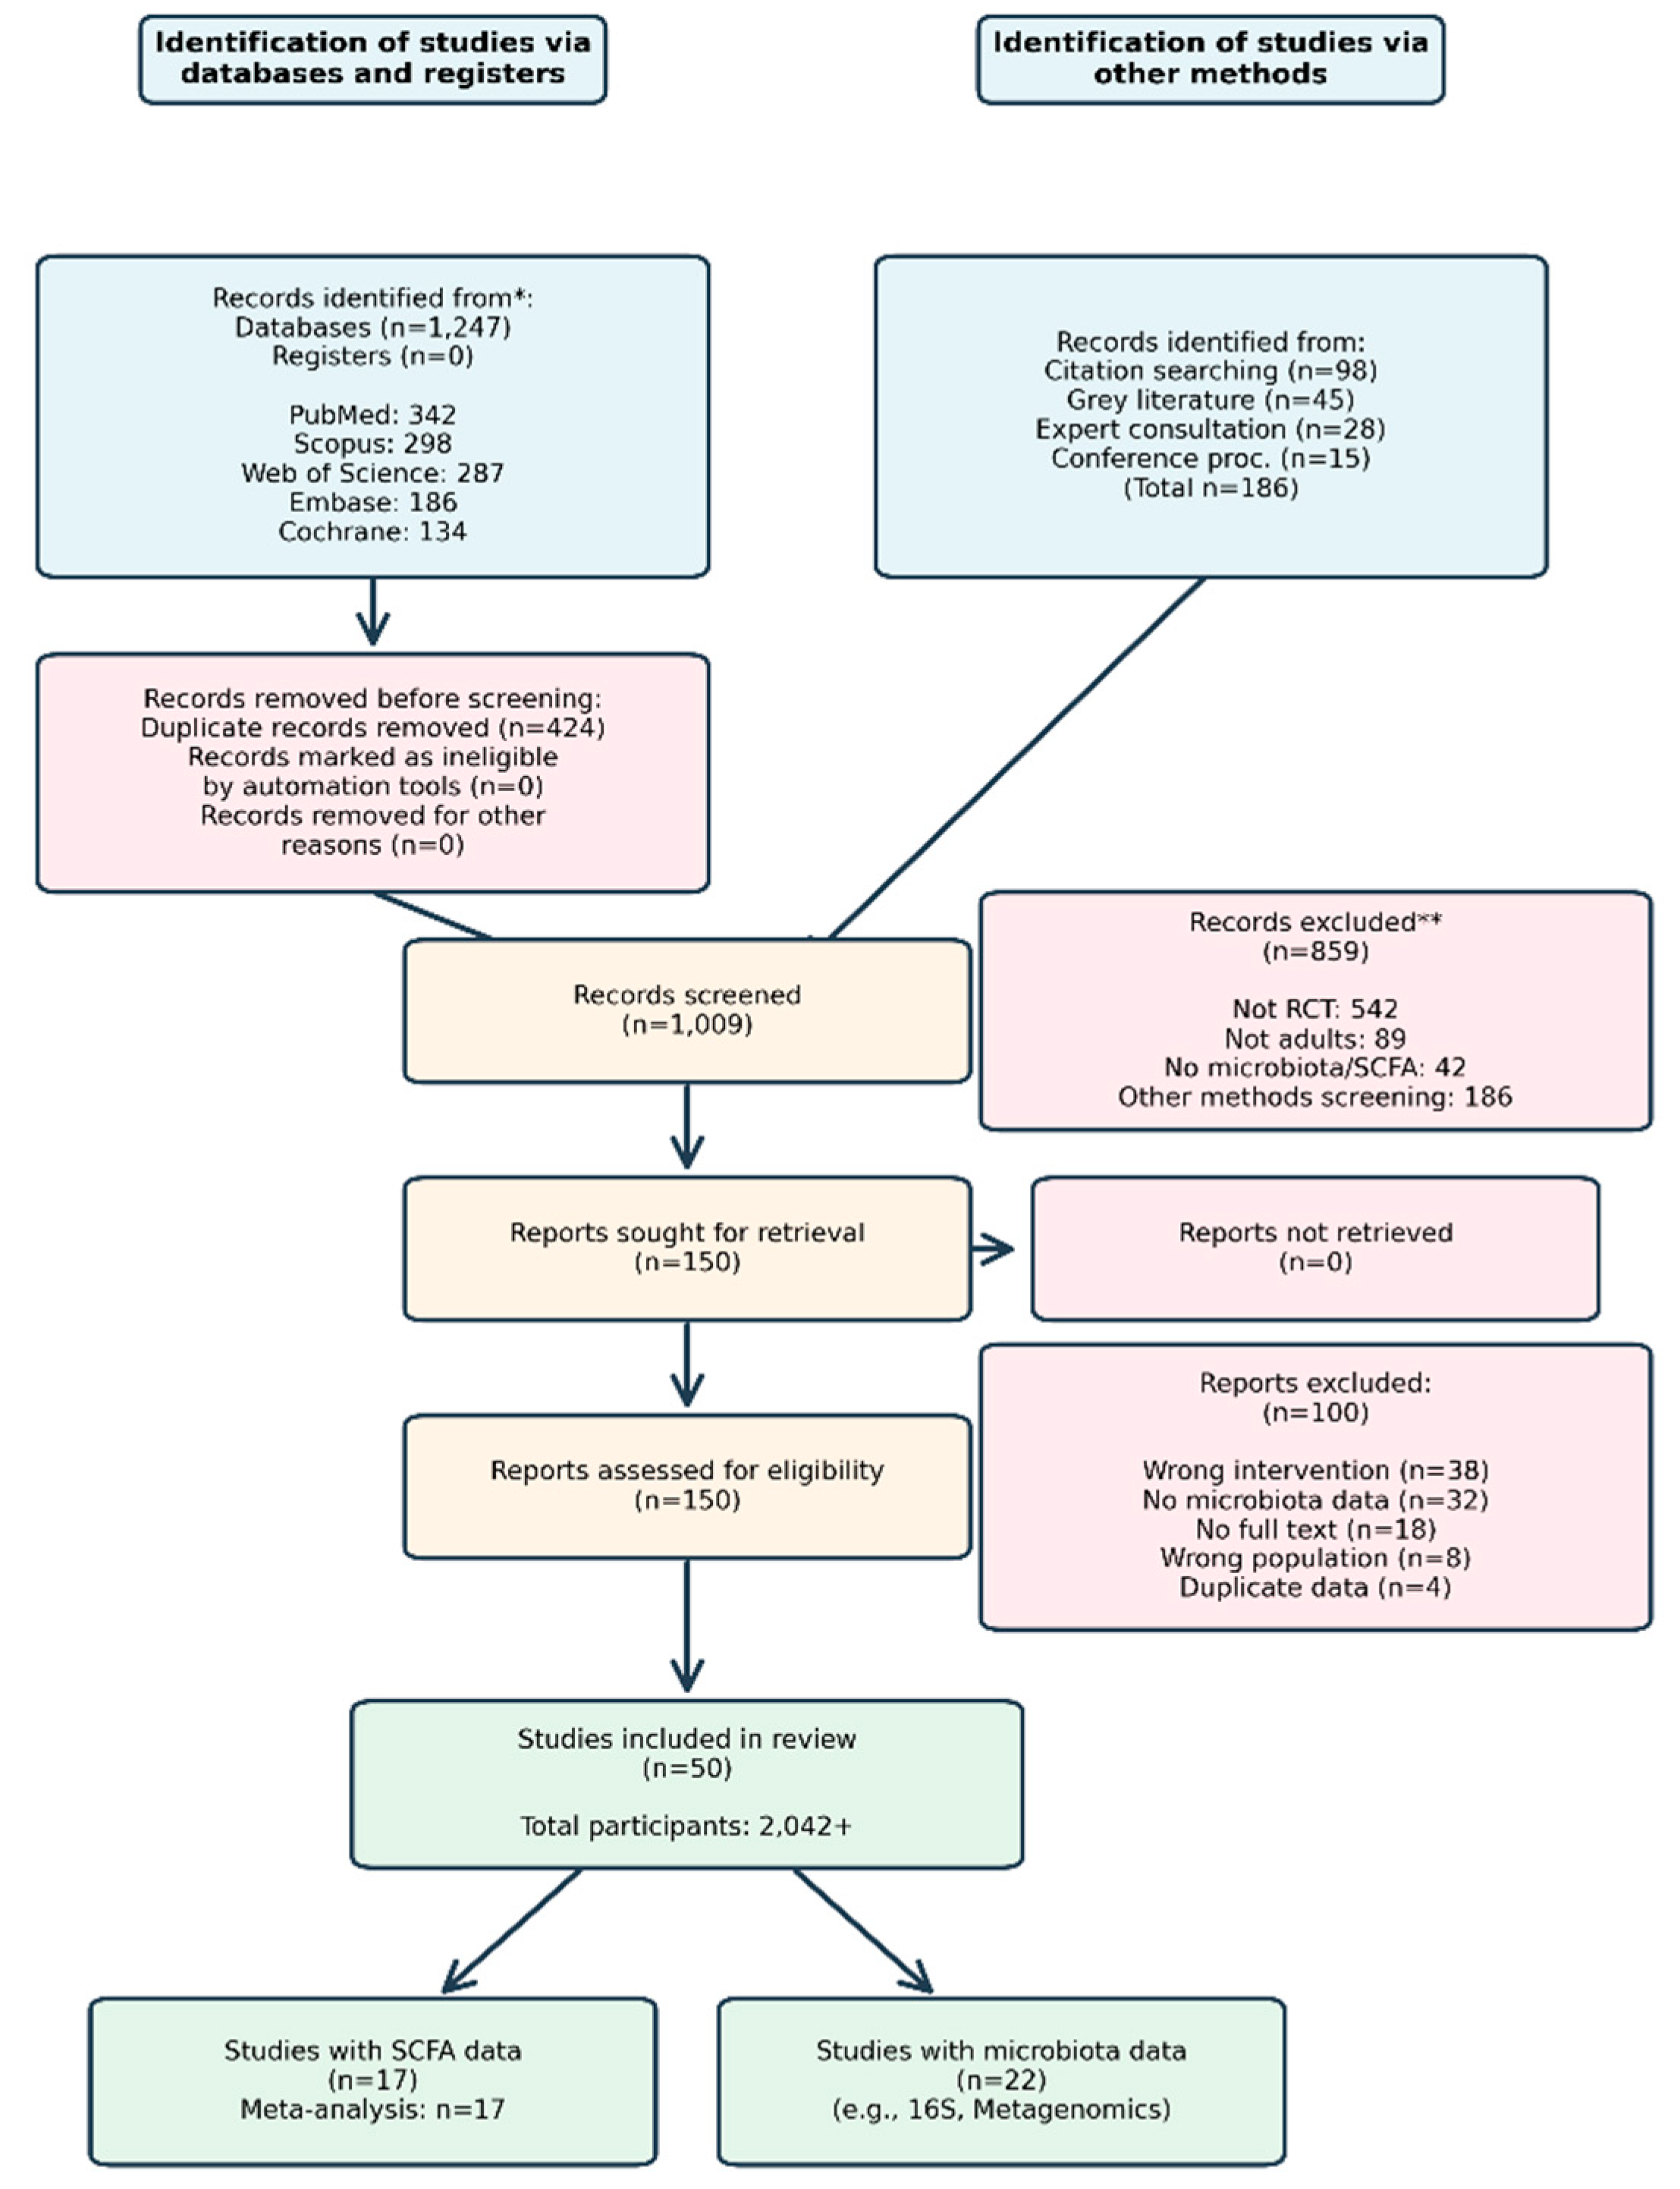
Figure 2.
Risk of Bias Assessment Across Included Randomized Controlled Trials. Summary of domain-level and overall risk-of-bias judgments using the Cochrane RoB 2 tool. Bars represent the proportion of studies rated as low risk, some concerns, or high risk across the five methodological domains.
Figure 2.
Risk of Bias Assessment Across Included Randomized Controlled Trials. Summary of domain-level and overall risk-of-bias judgments using the Cochrane RoB 2 tool. Bars represent the proportion of studies rated as low risk, some concerns, or high risk across the five methodological domains.
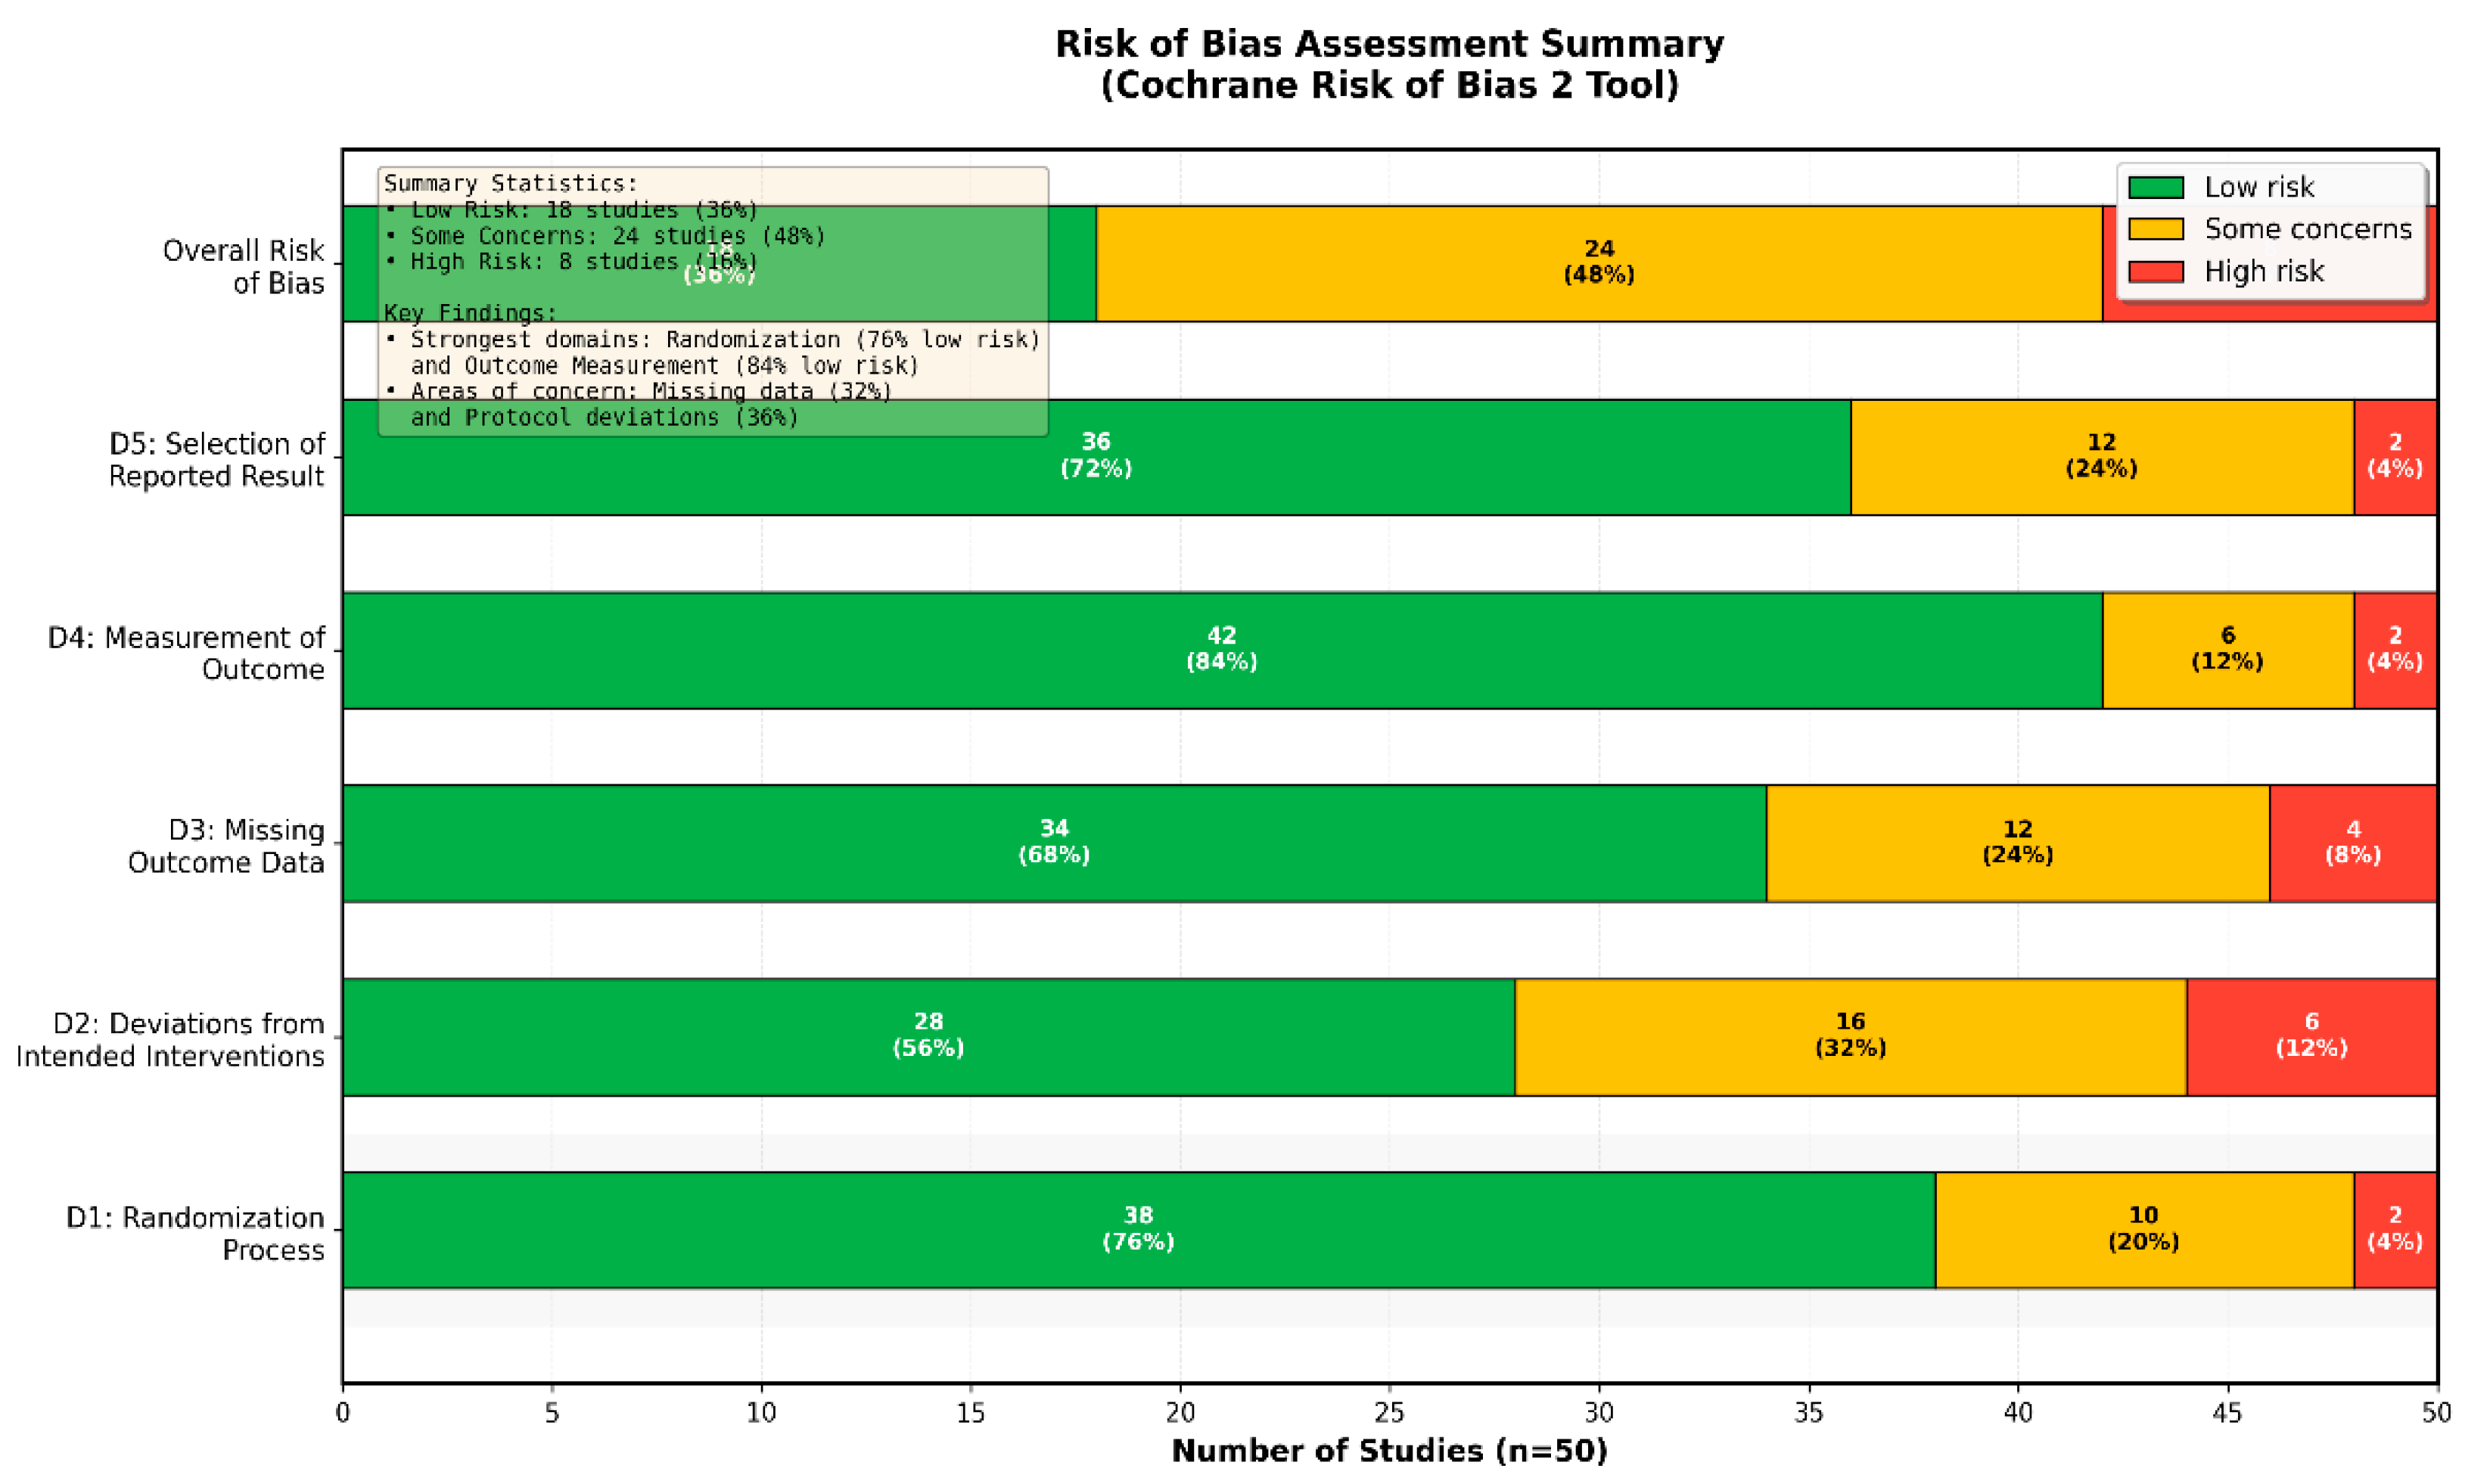
Figure 3.
Effects of Polyphenol Supplementation on Short-Chain Fatty Acid (SCFA) Production. (A) Distribution of study outcomes reporting increases, no change, or decreases in total SCFAs, acetate, propionate, and butyrate following polyphenol supplementation. (B) Mean percentage change from baseline for each SCFA, showing the range and median response across studies. (C) Mean absolute changes (µmol/g feces) in total SCFAs, acetate, propionate, and butyrate. (D) Standardized mean differences (SMDs) for butyrate and acetate stratified by study quality (low risk, some concerns, high risk), demonstrating consistent positive effects across methodological quality levels.
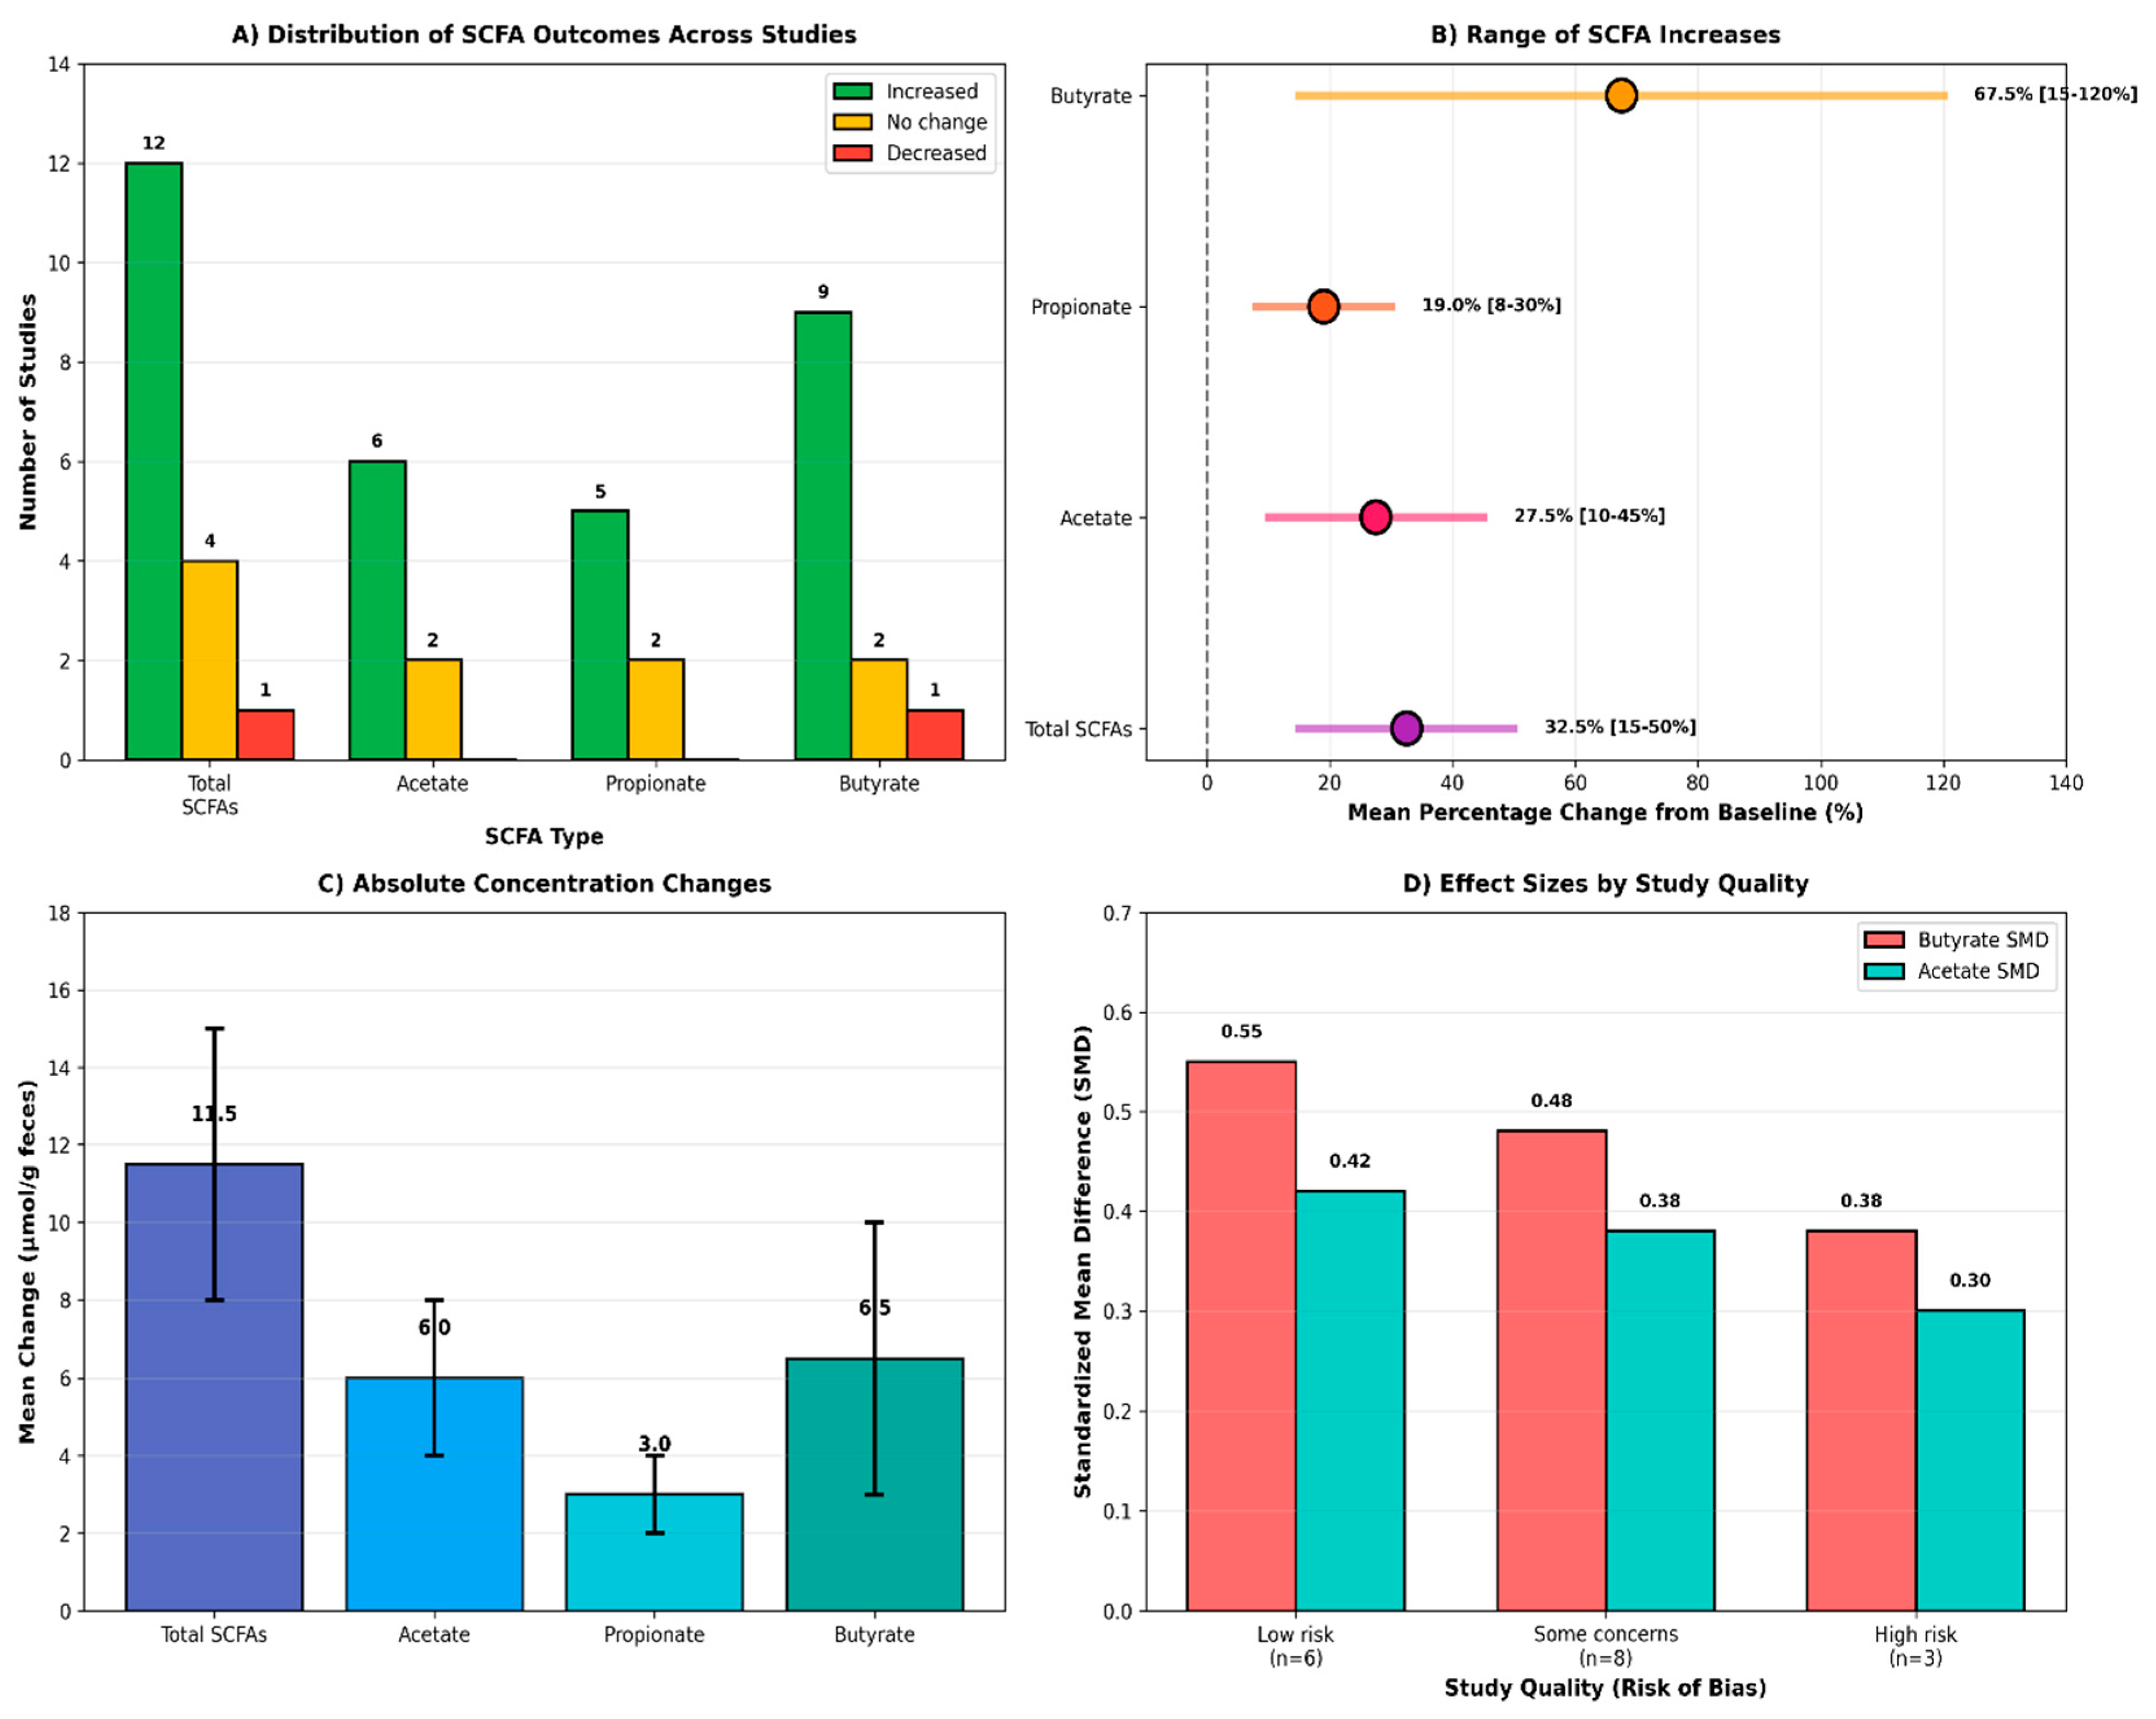
Figure 4.
Phylum-Level Changes in Gut Microbiota Following Polyphenol Supplementation. (A) Direction of phylum-level changes across 22 randomized controlled trials, showing the number of studies reporting decreased, unchanged, or increased abundances of Firmicutes, Bacteroidetes, Actinobacteria, Proteobacteria, and the Firmicutes/Bacteroidetes (F/B) ratio. (B) Heatmap illustrating representative percentage changes from baseline for four major phyla (Firmicutes, Bacteroidetes, Actinobacteria, Proteobacteria) across ten included studies. Color gradients reflect the magnitude and direction of change, with red indicating reductions and green indicating increases.
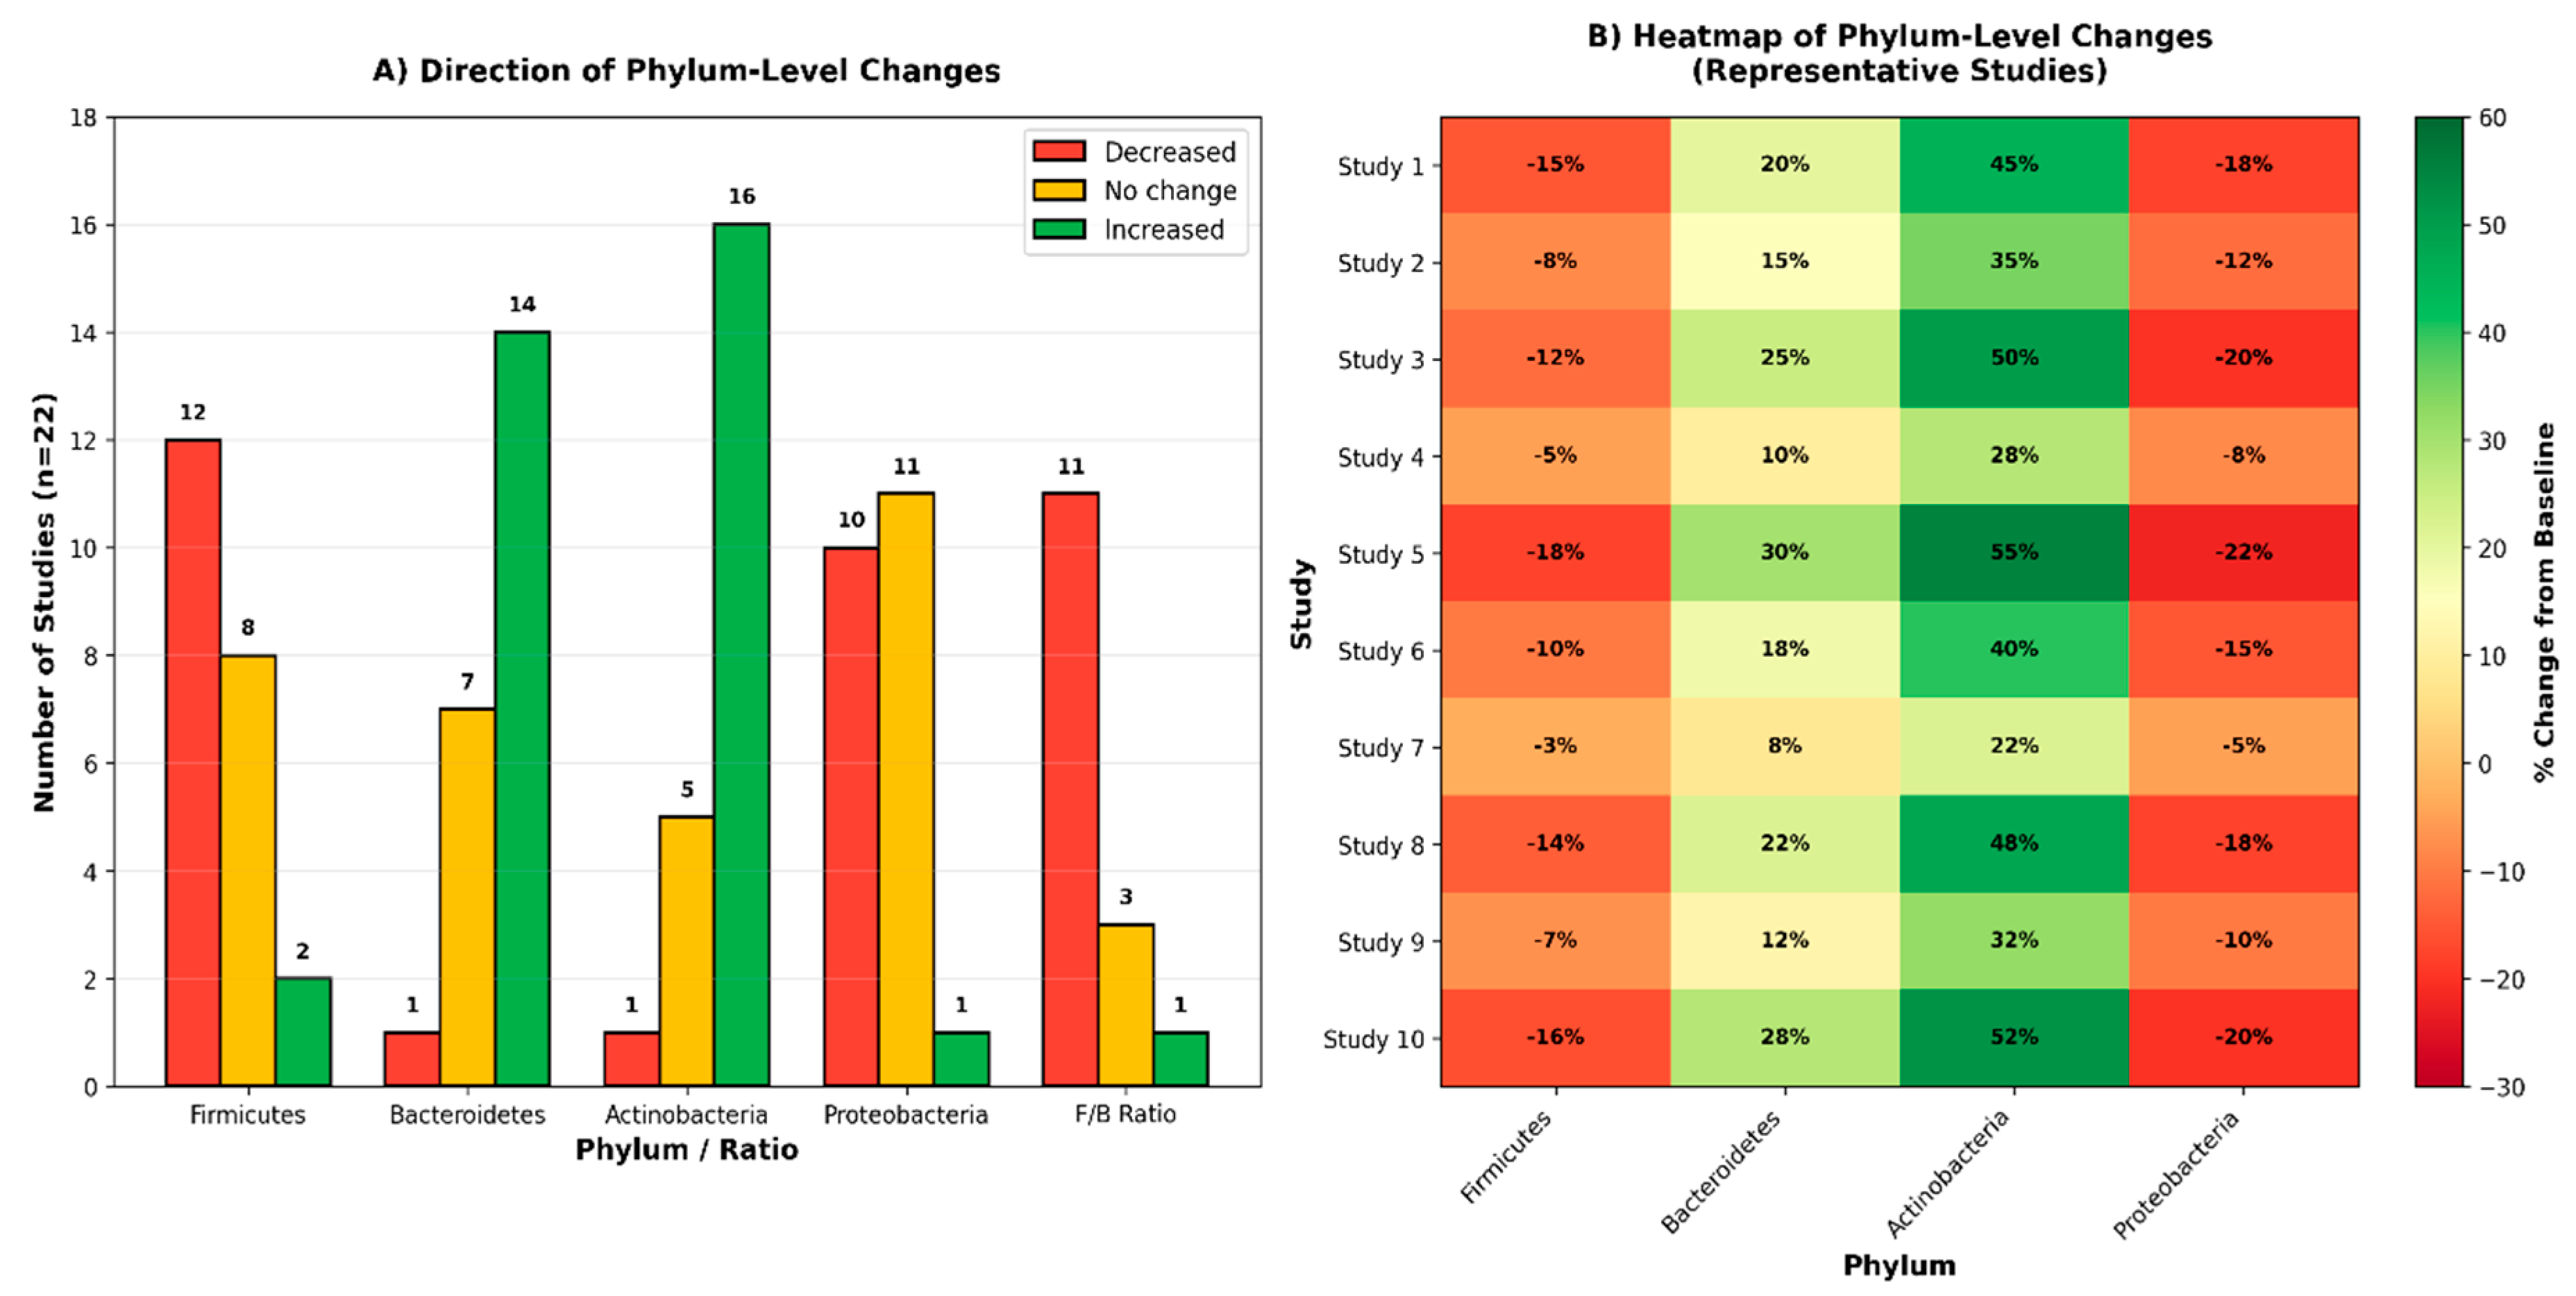
Figure 5.
Effects of Polyphenol Supplementation on Beneficial Bacterial Genera. (A) Proportion of randomized controlled trials reporting enrichment of key beneficial bacterial genera following polyphenol supplementation. The highest response rates were observed for Bifidobacterium (81.8%), Lactobacillus (54.5%), and Akkermansia muciniphila (50%). (B) Mean fold-change and corresponding range for each genus. Polyphenol supplementation produced the largest increases in Akkermansia muciniphila (mean 4.2×; range 2.0–8.5×) and Bifidobacterium (mean 2.5×; range 1.5–4.2×), with moderate increases observed for Faecalibacterium prausnitzii, Roseburia, Eubacterium, and Lactobacillus.
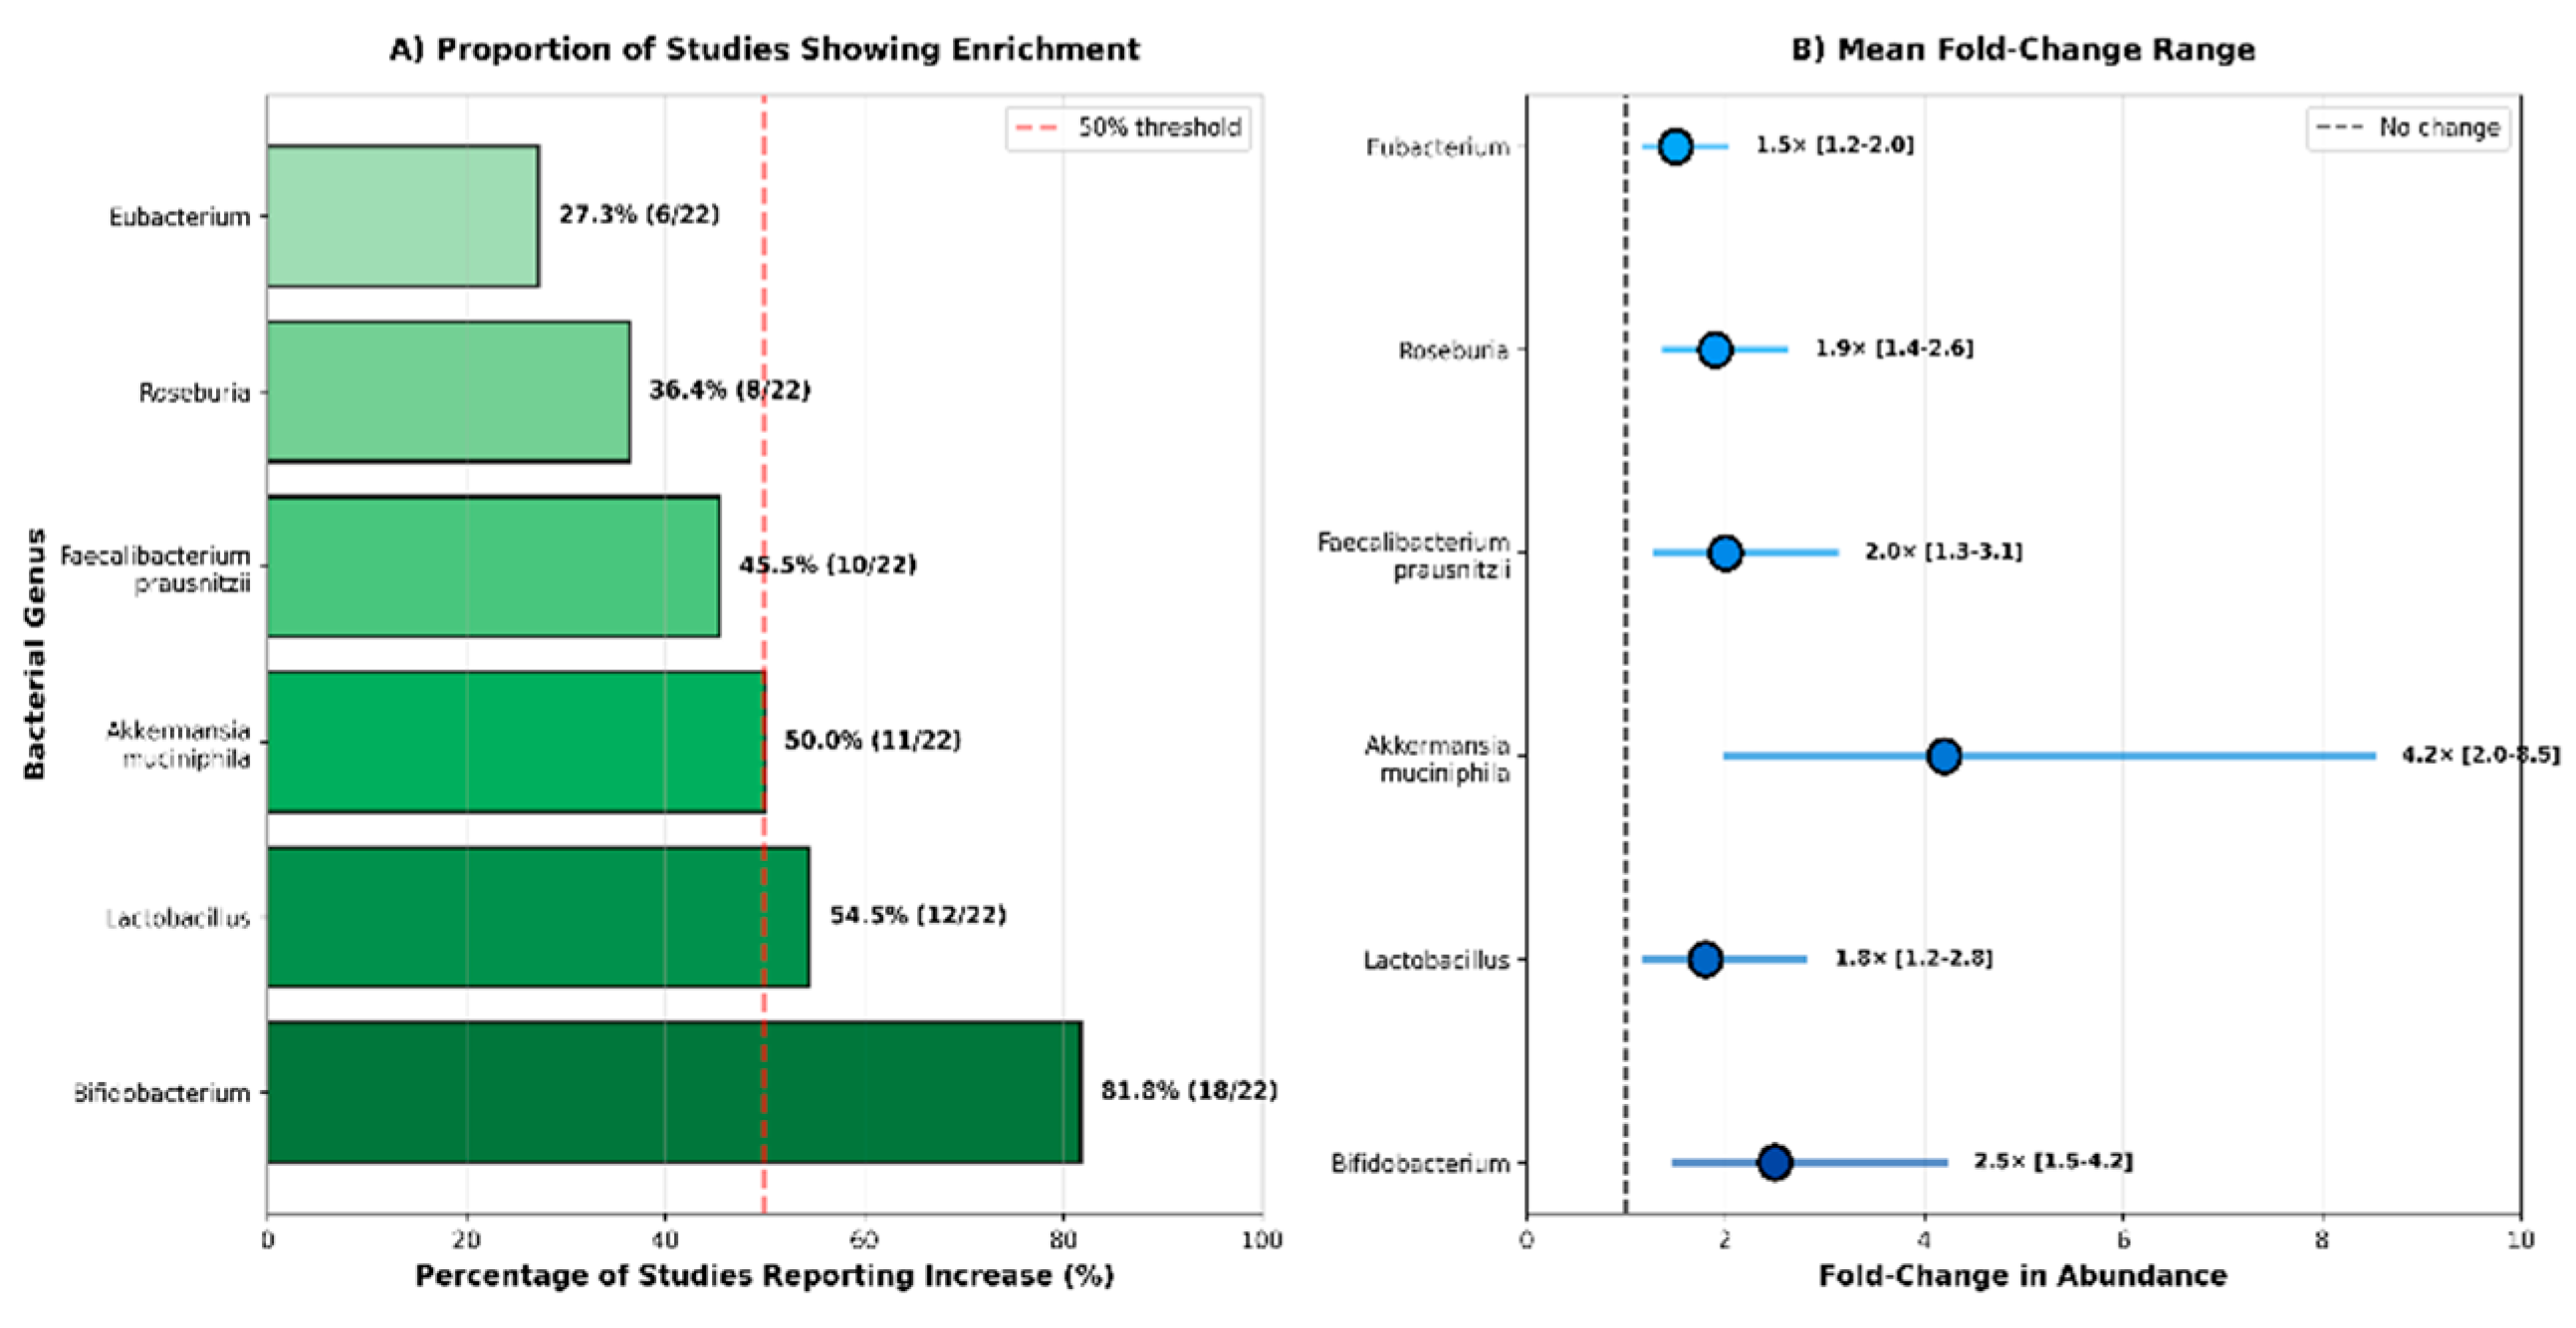
Figure 6.
Effects of Polyphenol Supplementation on Gut Microbiota Diversity. (A) Number of studies reporting increased, unchanged, or decreased alpha diversity across four commonly used metrics (Shannon, Simpson, Chao1, Observed Species). Most studies demonstrated increases in diversity following polyphenol supplementation. (B) Mean percentage change and range for each alpha diversity metric, showing moderate improvements in richness and evenness across studies. (C) Significance of beta diversity differences between intervention and control groups based on PERMANOVA results from 16 studies, indicating that polyphenol supplementation frequently produced significant or highly significant compositional shifts. (D) PERMANOVA R² values from 13 studies, representing the proportion of variance in microbial community structure explained by polyphenol supplementation. Most studies demonstrated moderate effect sizes (R² ≈ 0.2).
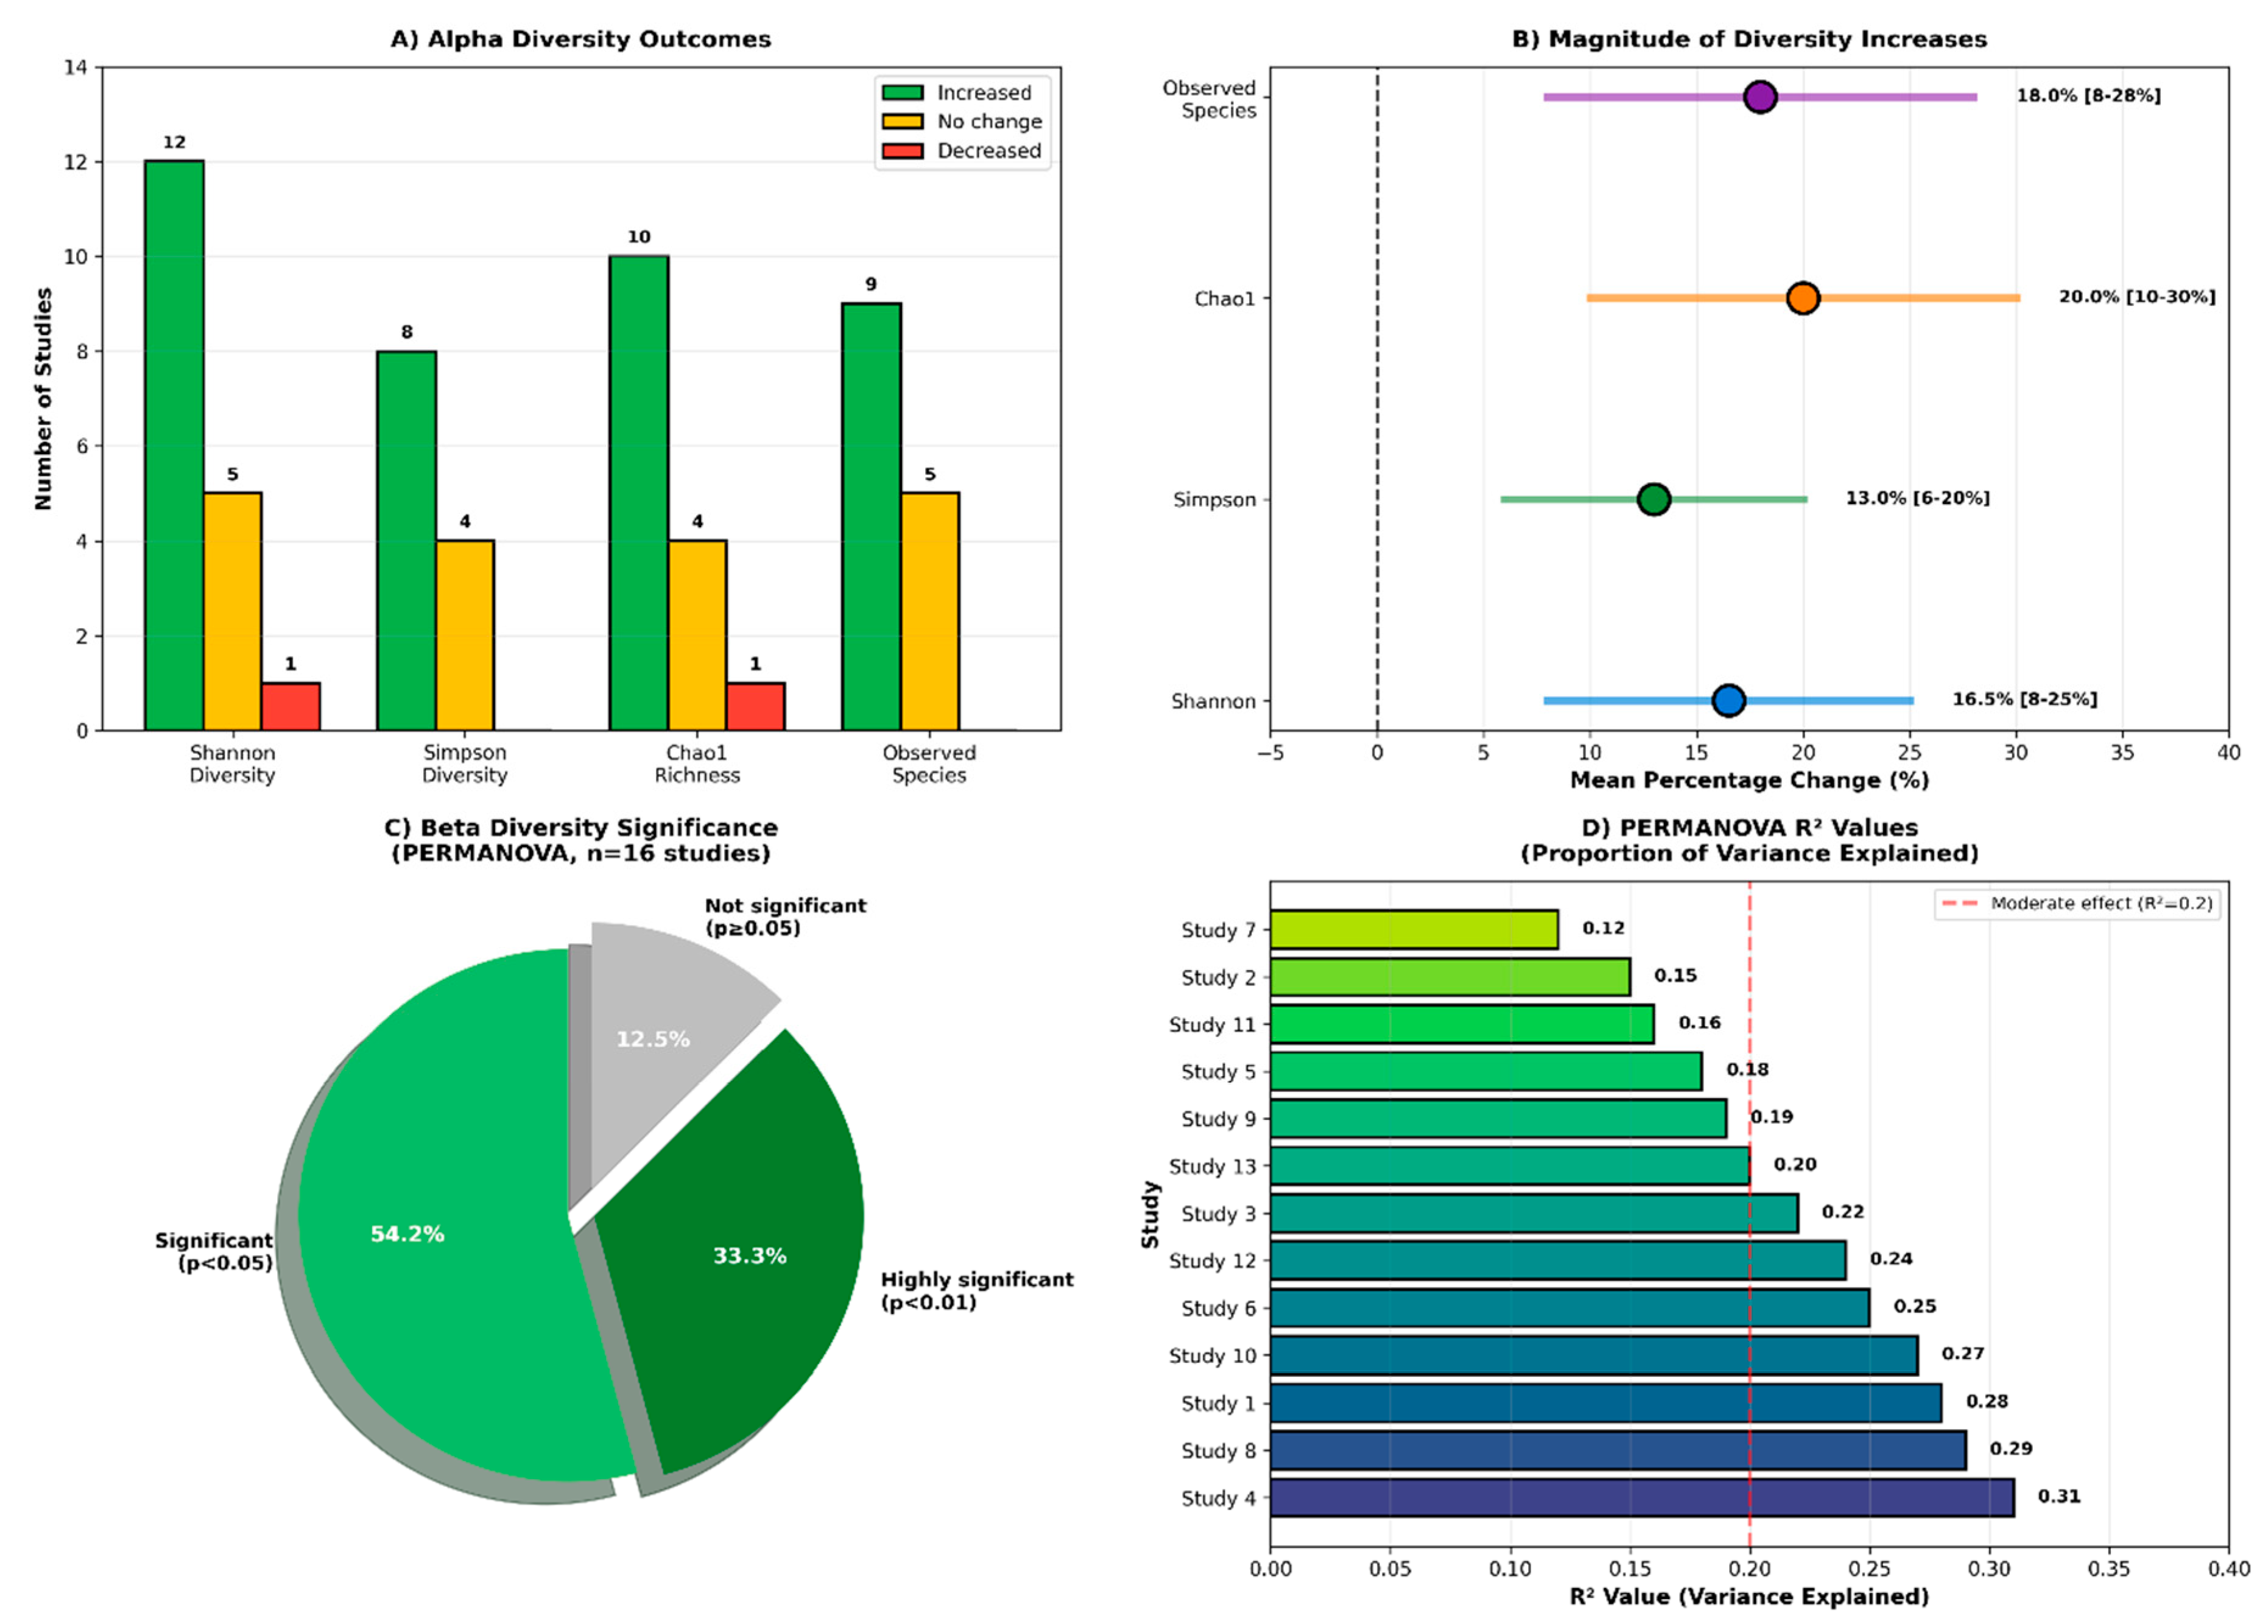
Figure 7.
Subgroup Analyses: Factors Influencing Polyphenol Effects on Gut Microbiota and SCFA Production.(A) Effect sizes (standardized mean differences, SMDs) for butyrate, Bifidobacterium, and Akkermansia muciniphila across polyphenol classes. Flavonoids and dietary fiber showed the strongest effects. (B) SCFA and microbiota effect sizes stratified by intervention duration. Medium-term (4–12 weeks) and long-term (>12 weeks) interventions produced larger and more consistent effects than short-term trials. (C) Mean effect sizes by baseline health status. Participants with metabolic syndrome or obesity exhibited greater responsiveness than healthy adults. (D) Dose–response relationship between polyphenol/fiber intake and butyrate production in dietary fiber studies, showing a positive polynomial trend. (E) Effect detection and taxonomic resolution across analytical methods. Metagenomics yielded higher effect sizes and resolution than 16S rRNA, qPCR, and culture-based techniques.
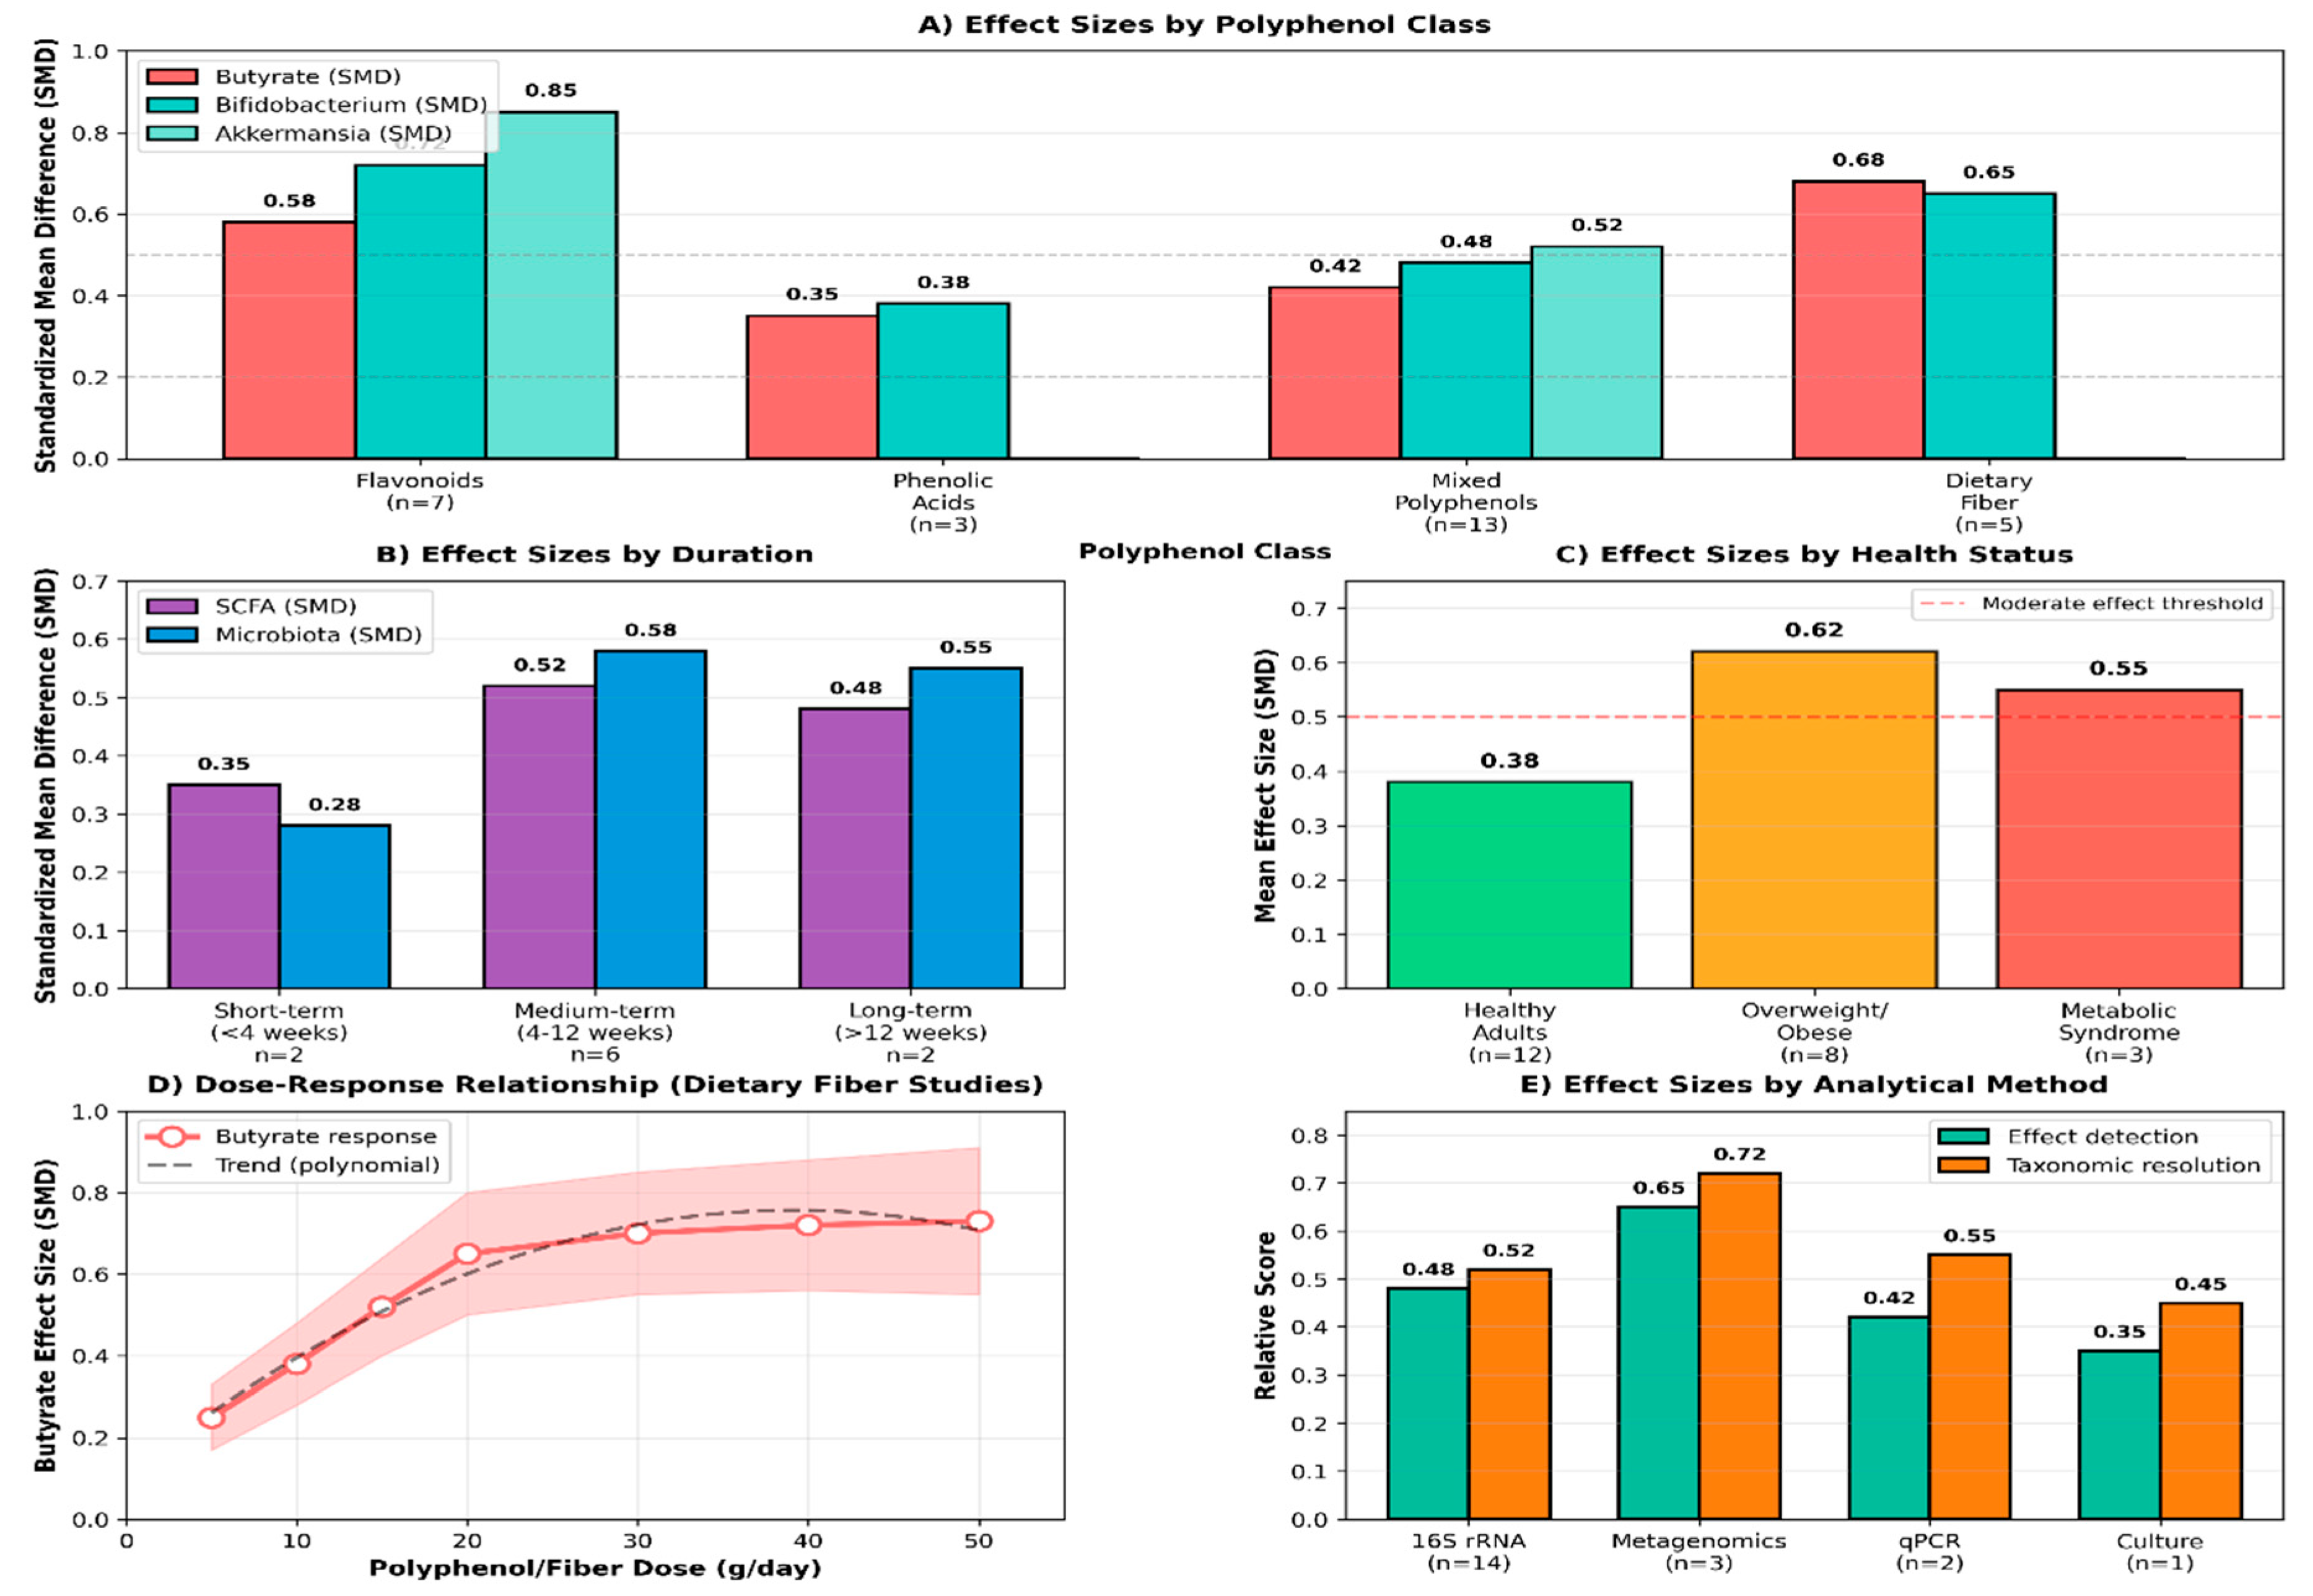
Figure 8.
Publication Bias Assessment and Sensitivity Analyses for the Butyrate Meta-Analysis. (A) Funnel plot assessing publication bias across included studies. The distribution of effect sizes appears symmetrical, and Egger’s test (p = 0.08) indicates no significant small-study effects. (B) Trim-and-fill analysis showing observed studies (blue) and imputed studies (red). The adjusted pooled effect (SMD = 0.42) remained consistent with the original estimate (SMD = 0.48), suggesting minimal influence of potential missing studies. (C) Leave-one-out sensitivity analysis demonstrating the robustness of the pooled effect. Removal of individual studies did not materially alter the overall SMD, indicating that no single study disproportionately influenced the results. (D) Cumulative meta-analysis ordered by publication year (2015–2023). The pooled effect stabilized over time, with later studies reinforcing the consistency and precision of the overall estimate.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.