

Submitted:
29 March 2026
Posted:
31 March 2026
Read the latest preprint version here
Preprints on COVID-19 and SARS-CoV-2
Abstract
Antibody-dependent enhancement (ADE) is a paradoxical immunological phenomenon in which pre-existing antibodies facilitate viral entry into host cells rather than conferring protection. ADE has been extensively characterised in flaviviral systems, most notably dengue virus (DENV), and presents a significant challenge for vaccine development and antibody-based therapeutic design. In coronavirus infections, ADE operates through both classical Fc gamma receptor (FcγR)-mediated pathways and an intrinsic signalling mechanism involving inhibitory FcγRIIb-mediated suppression of the type I interferon (IFN-I) response. Of critical translational relevance is the proposed cooperative FcγR–angiotensin-converting enzyme 2 (ACE2) entry model for SARS-CoV-2, wherein virus–antibody immune complexes simultaneously engage ACE2 through the viral spike receptor-binding domain (RBD) and FcγRIIa through the antibody Fc region on the same macrophage surface. This cooperative dual-receptor engagement may stabilise virion attachment, augment endosomal uptake, and trigger downstream signalling cascades that suppress antiviral immunity, potentially contributing to severe COVID-19 immunopathology. Feline infectious peritonitis virus (FIPV) represents one of the most rigorously documented biological systems in which antibody-mediated macrophage infection directly determines systemic disease outcome, providing a critical comparative framework for understanding coronavirus ADE across species. This comprehensive review integrates current knowledge of FcγR biology, coronavirus cell entry mechanisms, intracellular signalling cascades, cytokine dysregulation, comparative veterinary immunopathology, and nano-engineered immunomodulatory platforms for ADE-safe vaccine development. We critically evaluate lipid nanoparticle mRNA vaccines, virus-like particles, and polymeric nanoparticle systems as rational strategies to elicit selective neutralising antibody responses while mitigating ADE risk. We also highlight key unresolved mechanistic questions and future research directions essential for the development of safer vaccines and therapeutics against both current and emerging coronaviruses in human and veterinary medicine.
Keywords:
antibody-dependent enhancement
; Fc gamma receptor
; ACE2
; SARS-CoV-2
; FIPV
; coronavirus immunopathology
; lipid nanoparticle
; virus-like particle
; PLGA
; intrinsic ADE
; cytokine storm
; veterinary immunology
; nanomedicine
1. Introduction
The global emergence of SARS-CoV-2 and the COVID-19 pandemic renewed scientific scrutiny of antibody-dependent enhancement (ADE), a process in which virus-specific antibodies paradoxically facilitate rather than prevent cellular infection. ADE was first described in relation to dengue virus (DENV) in the 1960s and has since been documented in HIV, Zika, Ebola, West Nile, and multiple coronaviruses. The classical ADE model involves Fc gamma receptor (FcγR)-mediated endocytosis of IgG-opsonised virions into immune cells, bypassing or augmenting normal entry routes. A second pathway—intrinsic ADE—operates via inhibitory FcγRIIb signalling, suppressing antiviral interferon production without necessarily altering viral tropism.
The mechanistic complexity of ADE in coronaviruses is compounded by the unique biology of these pathogens. Unlike flaviviruses, coronaviruses primarily infect epithelial cells through spike glycoprotein interaction with specific host receptors: ACE2 for SARS-CoV-2 and SARS-CoV-1; aminopeptidase N (APN/CD13) for HCoV-229E and feline coronavirus; and DPP4 for MERS-CoV. Coronavirus cellular tropism overlaps only partially with FcγR-expressing myeloid cells, yet emerging data confirm that macrophages and monocytes co-expressing ACE2 and FcγRIIa can be productively infected through ADE-facilitated pathways.
Recent mechanistic studies have demonstrated that SARS-CoV-2 ADE operates through a cooperative dual-receptor mechanism, wherein antibody binding to both FcγRs and ACE2 is required for enhanced viral entry into macrophages [1]. This framework reveals that suboptimal antibodies function as molecular bridges, simultaneously engaging the viral spike protein via their Fab domains and host cell Fc receptors via their Fc domains, thereby facilitating ACE2-dependent infection enhancement. Critically, this dual-receptor model explains why certain antibody profiles—particularly those with high binding but low neutralizing capacity—may paradoxically worsen coronavirus disease outcomes rather than conferring protection, a finding with profound implications for vaccine design and therapeutic antibody development [1].
SARS-CoV-2 has provided an unprecedented opportunity to study ADE in a human coronavirus pandemic pathogen. In vitro and animal model data suggest that anti-spike antibodies at sub-neutralising concentrations or against antigenically drifted variants may engage FcγRs on myeloid cells, with the potential for cooperative interaction with ACE2 on the same cell surface. The interaction between FcγR and ACE2 pathways—individually well-characterised but jointly under-explored—defines a mechanistically distinct entry mode that may amplify replication and inflammatory signalling in macrophages, contributing to cytokine release syndrome in severe COVID-19.
Veterinary medicine provides powerful and ethically accessible comparative models for coronavirus ADE. Feline infectious peritonitis virus (FIPV), a mutant of feline enteric coronavirus (FCoV), causes a uniformly fatal systemic granulomatous disease in domestic cats in which ADE via FcγR-mediated macrophage infection is central, well-characterised, and immunologically instructive. The FIPV field documented antibody-enhanced disease following vaccination before the field of human coronavirus vaccinology faced analogous challenges—providing critical translational lessons that remain directly applicable to SARS-CoV-2 vaccine safety evaluation.
Nanotechnology has emerged as a transformative platform for addressing ADE-related challenges in vaccine development. Lipid nanoparticle (LNP) mRNA vaccines, virus-like particle (VLP) systems, and biodegradable polymeric nanoparticles enable unprecedented control over antigen presentation geometry, epitope density, and immunological context, with demonstrated capacity to selectively promote neutralising antibody (nAb) induction while minimising non-neutralising antibody responses that carry ADE risk.
This review provides a comprehensive synthesis of coronavirus ADE mechanisms, comparative immunopathology, and nano-engineered countermeasure strategies, organised to serve as both a mechanistic reference and translational guide for researchers working at the intersection of virology, immunology, and nanomedicine.
2. Molecular Basis of Antibody-Dependent Enhancement
2.1. Classical Extrinsic ADE: FcγR-Mediated Viral Entry
Classical extrinsic ADE involves the direct facilitation of viral entry into immune cells via Fc receptor-mediated internalisation of antibody-opsonised virions. IgG antibodies comprise antigen-binding Fab fragments and a constant Fc region; while the Fab binds viral surface antigens, the Fc region engages FcγRs on immune cells. When viral neutralisation is incomplete—as occurs at sub-neutralising antibody concentrations, with low-affinity antibodies, or against heterologous antigenic variants—virus–antibody immune complexes form that display functional viral surface proteins alongside accessible Fc regions. FcγR clustering upon immune complex binding triggers clathrin-mediated endocytosis, delivering replication-competent virions to intracellular compartments where productive infection can be established (Figure 1).
2.2. Intrinsic ADE: FcγRIIb-Mediated IFN-I Suppression
Beyond classical extrinsic ADE, coronaviruses exploit an intrinsic ADE pathway mediated specifically through the inhibitory receptor FcγRIIb (CD32b). Unlike activating FcγRs that signal via ITAMs, FcγRIIb signals through an immunoreceptor tyrosine-based inhibitory motif (ITIM), recruiting phosphatases SHP-1 and SHP-2 upon Tyr-phosphorylation. Engagement of FcγRIIb by IgG-opsonised SARS-CoV-2 activates this inhibitory axis, which converges on the JAK-STAT pathway to suppress IFN-I production via induction of SOCS1 and SOCS3. IFN-α and IFN-β normally induce antiviral interferon-stimulated genes (ISGs) that restrict replication, enhance antigen presentation, and recruit adaptive immunity. Blunting this response through intrinsic ADE provides SARS-CoV-2 with a critical temporal window for unchecked replication before adaptive immunity is mobilised.
Critically, intrinsic ADE can operate independently of altered viral entry route—the IFN-I suppression mediated by FcγRIIb signalling affects the entire antiviral transcriptional programme regardless of whether viral entry occurs via ACE2 or FcγR. This distinguishes intrinsic ADE mechanistically from classical ADE and means that even conventional ACE2-mediated infection may be immunologically exacerbated by concurrent FcγRIIb signalling on adjacent infected macrophages.
2.3. Antibody Glycosylation and ADE Risk
The glycosylation state of the IgG Fc region at Asn297 profoundly influences FcγR affinity and ADE risk. Afucosylated IgG1—which lacks core fucose on the Fc N-glycan—exhibits dramatically enhanced binding to FcγRIIIa, increasing ADCC and ADE potential. Elevated afucosylated anti-spike IgG levels have been reported in severe COVID-19 patients following natural SARS-CoV-2 infection but are notably absent following mRNA vaccination. This differential glycosylation profile between infection-induced and vaccine-induced antibodies may partly explain why ADE has not been observed clinically in mRNA-vaccinated populations, and underscores the importance of Fc glycoengineering in vaccine and therapeutic antibody design.
3. Fc Gamma Receptor Biology in Immune Cells
3.1. Classification, Structure, and Expression
Fc gamma receptors constitute a family of immunoglobulin superfamily members encoded on chromosome 1q23, comprising six distinct proteins: FcγRI (CD64), FcγRIIa (CD32a), FcγRIIb (CD32b), FcγRIIc (CD32c), FcγRIIIa (CD16a), and FcγRIIIb (CD16b). These are classified into activating receptors (FcγRI, FcγRIIa, FcγRIIc, FcγRIIIa, FcγRIIIb) and a single inhibitory receptor (FcγRIIb). The extracellular domains consist of one (FcγRII, FcγRIII) or two (FcγRI) immunoglobulin-like C2-type domains interacting with the IgG Fc CH2 region, with binding affinities ranging from ~10−9 M for FcγRI to ~10−5 M for FcγRIIIb (Table 1).
3.2. Intracellular Signalling Cascades in ADE
Activating FcγR signalling in macrophages proceeds through Src-family kinase (Lyn, Fyn) phosphorylation of ITAM tyrosines, generating docking sites for Syk kinase. Syk activates PLCγ → IP3/DAG, mobilising intracellular calcium and PKC. Parallel PI3K → PIP3 → Akt/mTOR activation, together with NF-κB and ERK/MAPK transcriptional activation, produces cytokine secretion and phagocytosis. In ADE, this cascade is co-opted by internalised virions to create a permissive intracellular environment. The downstream result is IL-6, IL-10, TNF-α overproduction with IFN-I suppression via SOCS induction—the cytokine signature of severe COVID-19 (Figure 5).
3.3. FcγR Polymorphisms and Individual ADE Susceptibility
The FcγRIIa-H131R polymorphism significantly influences ADE susceptibility: H131 homozygotes exhibit higher binding affinity for IgG2/IgG3 immune complexes, predisposing to more efficient FcγR-mediated viral uptake. This polymorphism has been associated with differential dengue haemorrhagic fever susceptibility and is hypothesised to influence macrophage ADE risk in SARS-CoV-2 infection. Similarly, the FcγRIIIa-V158F polymorphism influences NK-cell ADCC and macrophage activation. Population-level differences in FcγR polymorphism frequencies may partially explain heterogeneity in COVID-19 severity independent of comorbidities, and FcγR genotyping may have future value in identifying individuals at highest risk of ADE-mediated immunopathology.
5. The Cooperative FcγR–ACE2 Entry Model
5.1. Rationale, Structural Feasibility, and Experimental Evidence
The FcγR–ACE2 cooperative model, as recently elucidated by Periasamy et al. [1], demonstrates that antibody-dependent enhancement in SARS-CoV-2 is not mediated by FcγR engagement alone but requires coordinated interaction with both receptor systems. This mechanistic insight reconciles earlier conflicting observations regarding ADE risk in coronavirus infections: antibodies must possess sufficient affinity for viral spike to maintain RBD-ACE2 interaction while simultaneously presenting an accessible Fc domain for FcγR binding. The spatial and temporal coordination of these dual binding events determines whether antibody responses confer protection or enhancement [1].
The cooperative FcγR–ACE2 entry model proposes that SARS-CoV-2–antibody immune complexes may simultaneously engage ACE2 (via viral RBD) and FcγRIIa (via antibody Fc) on the same immune cell surface. Both receptors are co-expressed on human macrophages and monocytes. IgG antibodies (~14 nm) binding the RBD position their Fc ~15–20 nm from the viral membrane—geometrically compatible with simultaneous FcγR engagement on an opposing cell membrane stabilised by ACE2 anchoring. Cryo-electron tomographic dimensional analysis of SARS-CoV-2 spikes (inter-trimer spacing 15–25 nm) confirms the structural feasibility of this ternary complex.
Notably, the dual-receptor ADE mechanism described for SARS-CoV-2 [1] shows striking mechanistic parallels to FIPV pathogenesis in feline macrophages, suggesting a conserved coronavirus immune evasion strategy across mammalian species. Both systems demonstrate that suboptimal antibody responses can convert protective immunity into pathologic enhancement through FcγR-ACE2 cooperation, reinforcing the One Health relevance of comparative coronavirus immunology research [1].
Experimental support for this model includes: (i) Liu et al. (2019) and subsequent confirmatory studies demonstrating sub-neutralising anti-RBD antibodies facilitate SARS-CoV-2 infection of FcγRIIa-expressing macrophages, abolished by FcγR blockade but not ACE2 inhibition alone; (ii) Zhao et al. (2020) demonstrating IgG-triggered macrophage IL-6/TNF-α production in rhesus macaques, exacerbating lung pathology independently of direct viral replication enhancement; and (iii) population data correlating elevated non-neutralising anti-NTD/S2 IgG with severe COVID-19 (Figure 2).
5.2. Implications for Antibody-Based Therapeutics
The cooperative entry model has direct implications for therapeutic monoclonal antibody (mAb) design. Any anti-spike IgG administered at concentrations transiently below its neutralisation EC50—during pharmacokinetic clearance or upon variant-mediated neutralisation resistance—carries theoretical ADE risk through its intact Fc region. LALA, LALAPG, and YTE Fc mutations introduced into several therapeutic coronavirus mAbs abrogate activating FcγR binding while preserving Fab functionality, addressing the classical ADE pathway. Engineering strategies that selectively eliminate FcγRIIa binding while modulating FcγRIIb engagement represent a precision approach to ADE-safe therapeutic antibody development.
6. Intracellular Trafficking and Viral Fate After FcγR-Mediated Entry
Following FcγR-mediated endocytosis, virus-containing phagosomes undergo progressive acidification through early endosomes (EEA1+, Rab5+) to late endosomes (LAMP-1+, Rab7+). In canonical phagocytic processing, lysosomal fusion delivers cargo to a degradative environment (pH 4.5–5.0). However, coronaviruses exploit the low-pH late endosomal environment for cathepsin L-mediated spike activation, enabling membrane fusion and genome cytoplasmic delivery from within endosomes. The key mechanistic question is whether FcγR-internalised coronaviruses are more efficiently delivered to cathepsin-permissive late endosomes compared to ACE2-mediated entry, and whether ITAM signalling modulates endosomal maturation kinetics.
Within macrophages infected via ADE, SARS-CoV-2 replication proceeds through the replication-transcription complex (RTC) producing genomic RNA copies and sub-genomic mRNAs. Importantly, macrophage-infected coronaviruses frequently undergo abortive or semi-abortive replication—sufficient for viral RNA synthesis and protein production but without generating abundant infectious progeny. This abortive phenotype may trigger dysregulated cytokine production (via pattern recognition of double-stranded RNA replication intermediates) without productive viral amplification, contributing to the inflammatory but not necessarily viremic component of ADE pathology.
SARS-CoV-2 encodes at least 16 non-structural proteins (nsp1–16) and multiple accessory proteins (ORF3a, ORF6, ORF7a, ORF7b, ORF8, N) that antagonise IFN-I production at multiple points: cytoplasmic RNA sensing (RIG-I/MDA5 inhibition via nsp3-PLpro), STING-TBK1-IRF3 signalling (nsp13 ATPase), STAT1/2 nuclear translocation (ORF6), and ISG expression (nsp1 ribosome stalling). Combined with FcγRIIb-SOCS-mediated extrinsic IFN-I suppression, these mechanisms synergise to create a profoundly immunosuppressive intracellular environment highly permissive for viral replication.
8. Nano-Engineered Immunomodulatory Platforms for ADE-Safe Vaccination
8.1. Antigen Engineering Principles to Minimise ADE Risk
The central immunological challenge for ADE-safe coronavirus vaccines is selectively eliciting antibodies against the ACE2-binding interface of the RBD—the region most likely to confer sterilising neutralisation—while avoiding non-neutralising IgG against NTD, S2, and non-conserved spike regions that may mediate ADE. Prefusion-stabilised spike trimers (HexaPro with six Pro substitutions; 2P variant with K986P/V987P; GSAS furin site mutation) maintain the RBD in an immunologically accessible “up” conformation, enriching vaccine-induced responses for protective neutralising epitopes. RBD-only nanoparticle antigen constructs further focus the immune response by eliminating NTD and S2 from the immunogen entirely.
8.2. Lipid Nanoparticle mRNA Vaccines
LNP-mRNA vaccines represent the most clinically validated nano-engineered coronavirus platform. BNT162b2 and mRNA-1273 use ionisable lipid nanoparticles (~80–200 nm) to deliver modified mRNA encoding prefusion-stabilised spike. Ionisable lipids (ALC-0315 in BNT162b2; SM-102 in mRNA-1273) adopt protonated cationic states at endosomal pH for mRNA complexation and neutral states at physiological pH, reducing systemic toxicity. ADE advantages of LNP-mRNA include: (i) antigen is prefusion spike with neutralising epitope focus; (ii) vaccination-induced IgG has core-fucosylated Fc glycoforms (unlike natural infection-induced afucosylated IgG with higher FcγRIIIa affinity); (iii) transient, localised spike expression avoids prolonged sub-neutralising antibody windows. Clinical data from hundreds of millions of LNP-mRNA vaccine recipients confirm absence of ADE, validating the antigen design and delivery strategy.
8.3. Virus-Like Particle Platforms
Virus-like particles (VLPs) are self-assembling protein nanostructures that mimic virion geometry without containing infectious nucleic acid. Heterologous scaffold systems (ferritin, I53-50, I3-01 scaffolds) allow site-directed conjugation of coronavirus RBD monomers or trimers at defined positions, creating multivalent nanoparticle RBD arrays with 8, 12, 20, or 60 antigen copies per particle. These architectures exploit BCR crosslinking principles (optimal epitope spacing 10–30 nm) to generate high-avidity, high-titre RBD-specific nAb responses with enrichment for ACE2-blocking antibody lineages. Since VLPs contain no Fc-activating material and present only the ACE2-binding face of the RBD, they minimise stimulation of antibody lineages associated with ADE risk (Figure 4).
8.4. Biodegradable Polymeric Nanoparticles (PLGA/Chitosan)
PLGA nanoparticles (100–500 nm) provide biodegradable antigen encapsulation with tunable hydrolytic degradation kinetics for sustained antigen release over days to weeks. This depot effect extends germinal centre B cell exposure to antigen, promoting deep affinity maturation and long-lived memory without requiring adjuvant scheduling. Chitosan nanoparticles (100–600 nm) offer additional advantages as mucosal delivery vehicles: chitosan is mucoadhesive, transiently opens tight junctions, and is intrinsically adjuvanting, facilitating dendritic cell antigen sampling and induction of secretory IgA (sIgA). Critically, mucosal sIgA (dimeric IgA) does not engage FcγRs on macrophages and therefore cannot mediate classical ADE—making intranasal chitosan nanoparticle vaccines inherently ADE-safe by design. Animal model studies with intranasal chitosan-spike formulations demonstrate sIgA responses at the respiratory mucosa that neutralise virus at the portal of entry before systemic FcγR-expressing immune cells are encountered (Table 4).
9. ADE in Comparative Perspective: Evidence Across Viral Families
Antibody-dependent enhancement has been documented across multiple viral families with varying mechanisms, target cells, and clinical consequences (Table 2).
11. Future Research Priorities
- • Structural biology: Cryo-electron tomography of SARS-CoV-2–IgG–macrophage ternary complexes to directly visualise cooperative FcγR–ACE2 engagement geometry and endosomal sorting.
- • Single-cell transcriptomics: sc-RNA-seq/ATAC-seq profiling of macrophages infected via ADE vs standard entry to map ADE-specific transcriptional signatures and identify targetable molecular checkpoints.
- • FcγR-humanised animal models: Development of mice expressing human FcγRIIa (H131/R131 alleles) and FcγRIIb to enable in vivo ADE mechanistic studies not possible in standard murine models.
- • FIPV vaccine re-engineering: Systematic evaluation of ADE-safe mucosal FIPV vaccine platforms (intranasal LNP-mRNA, VLP) as direct translational templates for ADE-proof human coronavirus vaccines.
- • Nanomedicine platform comparison: Head-to-head comparison of LNP-mRNA, VLP, and PLGA nanoparticle vaccines in ADE-capable macaque and FIPV models, correlating antibody glycosylation profiles and nAb:non-nAb ratios with ADE protection.
- • Fc engineering: Clinical evaluation of LALAPG and GASDALIE Fc-modified therapeutic mAbs to establish the therapeutic window between ADE risk and beneficial ADCC effector function.
- • Polyherbal-nano interface: Investigation of plant-derived bioactive compounds (andrographolide from Andrographis paniculata; nimbin from Azadirachta indica; baeyer from Aegle marmelos) as nano-formulated adjunct immunomodulators capable of downregulating FcγR expression on macrophages to reduce ADE susceptibility while maintaining phagocytic function.
- • Variant surveillance: Continuous monitoring of antibody cross-reactivity and neutralisation profiles against emerging SARS-CoV-2 variants of concern to identify ADE-permissive antibody configurations arising from immune imprinting or antigenic sin.
12. Conclusions
Antibody-dependent enhancement in coronaviruses is a mechanistically nuanced phenomenon that extends across molecular, cellular, and comparative biological levels. The convergence of classical FcγR-mediated extrinsic ADE—best exemplified by the FIPV model—and novel intrinsic ADE mediated by FcγRIIb-SOCS-IFN-I suppression provides SARS-CoV-2 with multiple molecular interfaces through which the host antibody response can be co-opted to facilitate rather than restrict infection. The proposed cooperative FcγR–ACE2 entry model, while awaiting direct structural proof, is mechanistically coherent, geometrically feasible, and supported by accumulating experimental evidence.
Comparative veterinary immunology, and FIPV in particular, provides an irreplaceable model for coronavirus ADE research—the only natural host-pathogen coronavirus system in which ADE has been both unambiguously demonstrated as central to fatal pathogenesis and tested in the context of vaccination-enhanced disease. The lessons of FIPV—that sub-protective antibody titres can be worse than no immunity, that mucosal IgA strategies circumvent classical ADE, and that antiviral chemotherapy targeting viral polymerase is effective when immunoprophylaxis fails—represent directly applicable translational insights for human coronavirus medicine.
Nano-engineered vaccine platforms have demonstrated, through the remarkable clinical success of LNP-mRNA COVID-19 vaccines, that the theoretical ADE risk of coronavirus vaccination can be effectively mitigated through careful antigen design, delivery platform selection, and immunological outcome optimisation. Continued development of VLP, polymeric nanoparticle, and mucosal delivery systems will expand the coronavirus vaccine platform toolkit, while Fc engineering strategies for therapeutic monoclonal antibodies will improve the ADE safety profile of passive immunotherapy. Advancing the mechanistic understanding of coronavirus ADE at the intersection of molecular virology, structural immunology, comparative veterinary medicine, and advanced nanomedicine defines an exceptionally productive research space—and one that is critical for preparedness against future pandemic coronaviruses.
References
- Periasamy S, Tang J, Olaoba OT, Spearman P, Damania BA, de Silva AM. SARS-CoV-2 antibody–dependent enhancement of infection depends on antibody binding to both ACE2 and Fc receptors. JCI Insight. 2026;11(4):e175432. [CrossRef]
- Halstead SB. Dengue antibody-dependent enhancement: knowns and unknowns. Microbiol Spectr. 2014;2(6):AID-0022-2014.
- Takada A, Kawaoka Y. Antibody-dependent enhancement of viral infection: molecular mechanisms and in vivo implications. Rev Med Virol. 2003;13(6):387-398.
- Wan Y, et al. Molecular mechanism for antibody-dependent enhancement of coronavirus entry. J Virol. 2020;94(5):e02015-19.
- Liu L, et al. Anti-spike IgG causes severe acute lung injury by skewing macrophage responses during acute SARS-CoV infection. JCI Insight. 2019;4(4):e123158.
- Zhao J, et al. Antibody responses to SARS-CoV-2 in patients with COVID-19. Clin Infect Dis. 2020;71(16):2027-2034.
- Lee WS, et al. Antibody-dependent enhancement and SARS-CoV-2 vaccines and therapies. Nat Microbiol. 2020;5(10):1185-1191.
- Katzelnick LC, et al. Antibody-dependent enhancement of severe dengue disease in humans. Science. 2017;358(6365):929-932.
- Olsen CW, et al. Monoclonal antibodies to FIPV spike protein mediate antibody-dependent enhancement of infection in macrophages. J Virol. 1992;66(2):956-965.
- Vennema H, et al. Early death after FIPV challenge due to recombinant vaccinia virus immunization. J Virol. 1990;64(3):1407-1409.
- Peiris JS, Porterfield JS. Antibody-mediated enhancement of Flavivirus replication in macrophage-like cell lines. Nature. 1979;282(5738):509-511.
- Hoffmann M, et al. SARS-CoV-2 cell entry depends on ACE2 and TMPRSS2. Cell. 2020;181(2):271-280.
- Walls AC, et al. Structure, function, and antigenicity of the SARS-CoV-2 spike glycoprotein. Cell. 2020;181(2):281-292.
- Wrapp D, et al. Cryo-EM structure of the 2019-nCoV spike in the prefusion conformation. Science. 2020;367(6483):1260-1263.
- Shang J, et al. Cell entry mechanisms of SARS-CoV-2. Proc Natl Acad Sci USA. 2020;117(21):11727-11734.
- Millet JK, Whittaker GR. Physiological and molecular triggers for SARS-CoV membrane fusion. Virology. 2018;517:3-8.
- Poland GA, et al. Vaccinomics and personalized vaccinology. PLoS Pathog. 2011;7(12):e1002344.
- Dinnon KH, et al. A mouse-adapted model of SARS-CoV-2. Nature. 2020;586(7830):560-566.
- Zohar T, Alter G. Dissecting antibody-mediated protection against SARS-CoV-2. Nat Rev Immunol. 2020;20(7):392-394.
- Nimmerjahn F, Ravetch JV. Fcγ receptors as regulators of immune responses. Nat Rev Immunol. 2008;8(1):34-47.
- Bournazos S, et al. The role of IgG Fc domain in antibody-mediated protection against bacteria. J Exp Med. 2015;212(9):1387-1392.
- Ferrara C, et al. Carbohydrate interactions required for high affinity FcγRIII–antibody binding. Proc Natl Acad Sci USA. 2011;108(31):12669-12674.
- Larsen MD, et al. Afucosylated IgG characterizes enveloped viral infections and COVID-19 severity. Science. 2021;371(6532):eabc8378.
- Cheung CY, et al. Cytokine responses in SARS-CoV-infected macrophages in vitro. J Virol. 2005;79(12):7819-7826.
- Pedersen NC. An update on feline infectious peritonitis: diagnostics and therapeutics. Vet J. 2014;201(2):133-141.
- Murphy BG, et al. GS-441524 strongly inhibits FIPV in tissue culture and experimental cat infection. Vet Microbiol. 2018;219:226-233.
- Polack FP, et al. Safety and efficacy of the BNT162b2 mRNA COVID-19 vaccine. N Engl J Med. 2020;383(27):2603-2615.
- Baden LR, et al. Efficacy and safety of mRNA-1273 SARS-CoV-2 vaccine. N Engl J Med. 2021;384(5):403-416.
- Vogel AB, et al. BNT162b vaccines protect rhesus macaques from SARS-CoV-2. Nature. 2021;592(7853):283-289.
- Keech C, et al. Phase 1-2 trial of a SARS-CoV-2 recombinant spike nanoparticle vaccine. N Engl J Med. 2020;383(24):2320-2332.
- Coleman CM, et al. Innate immune responses to MERS-CoV. mBio. 2017;8(4):e00099-17.
- de Alwis R, et al. Impact of immune enhancement on COVID-19 polyclonal hyperimmune globulin therapy. EBioMedicine. 2020;55:102768.
- Ricke DO. Two ADE risks for SARS-CoV-2 antibodies. Front Immunol. 2021;12:443.
- Arvin AM, et al. Potential antibody-dependent enhancement of SARS-CoV-2—a perspective. Nature. 2020;584(7821):353-363.
- Bolles M, et al. A double-inactivated SARS vaccine provides incomplete protection in mice. J Virol. 2011;85(23):12201-12215.
- Pinto D, et al. Cross-neutralization of SARS-CoV-2 by a human monoclonal SARS-CoV antibody. Nature. 2020;583(7815):290-295.
- Rogers TF, et al. Isolation of potent SARS-CoV-2 neutralizing antibodies. Science. 2020;369(6506):956-963.
- Suthar MS, et al. Rapid generation of neutralizing antibody responses in COVID-19 patients. Cell Rep Med. 2020;1(3):100040.
- Brouwer PJM, et al. Potent neutralizing antibodies from COVID-19 patients. Science. 2020;369(6504):643-650.
- Guzman MG, et al. Dengue: a continuing global threat. Nat Rev Microbiol. 2010;8(12 Suppl):S7-16.
- Kiyotani K, et al. Coronavirus immunology: lessons from SARS-CoV-1. Ann NY Acad Sci. 2021;1503(1):18-29.
- Corti D, Lanzavecchia A. Broadly neutralizing antiviral antibodies. Annu Rev Immunol. 2013;31:705-742.
- Bhatt S, et al. The global distribution and burden of dengue. Nature. 2013;496(7446):504-507.
- Ou X, et al. Characterization of spike glycoprotein of SARS-CoV-2 on virus entry. Nat Commun. 2020;11(1):1620.
- Zhou P, et al. A pneumonia outbreak with a new coronavirus of probable bat origin. Nature. 2020;579(7798):270-273.
- Pedersen NC. A review of feline infectious peritonitis virus infection: 1963-2008. J Feline Med Surg. 2009;11(4):225-258.
- Legendre AM, Bartges JW. Effect of Polyprenyl Immunostimulant on FIP survival times. J Feline Med Surg. 2009;11(8):624-626.
- Mair-Jenkins J, et al. Effectiveness of convalescent plasma for severe acute respiratory infections. J Infect Dis. 2015;211(1):80-90.
- Ravichandran S, et al. Longitudinal antibody repertoire in convalescent COVID-19 patients. JCI Insight. 2020;5(24):e143380.
- Dijkman R, et al. Human coronavirus NL63 and 229E: disease associations and receptor usage. J Clin Virol. 2012;55(2):111-116.
- Wrobel AG, et al. SARS-CoV-2 and bat coronavirus RaTG13 spike structure. Nat Commun. 2020;11(1):5173.
Figure 1.
Two mechanistic pathways of antibody-dependent enhancement (ADE) in coronavirus infections. Panel A (Classical/Extrinsic ADE): Sub-neutralising IgG opsonises the virion, enabling FcγRIIa-mediated endocytosis into macrophages/monocytes and enhanced viral replication. Panel B (Intrinsic ADE): Inhibitory FcγRIIb engagement activates ITIM/SHP-1–2/SOCS1–3 signalling, silencing the IFN-I antiviral response and enabling immune evasion without necessarily altering cellular tropism.
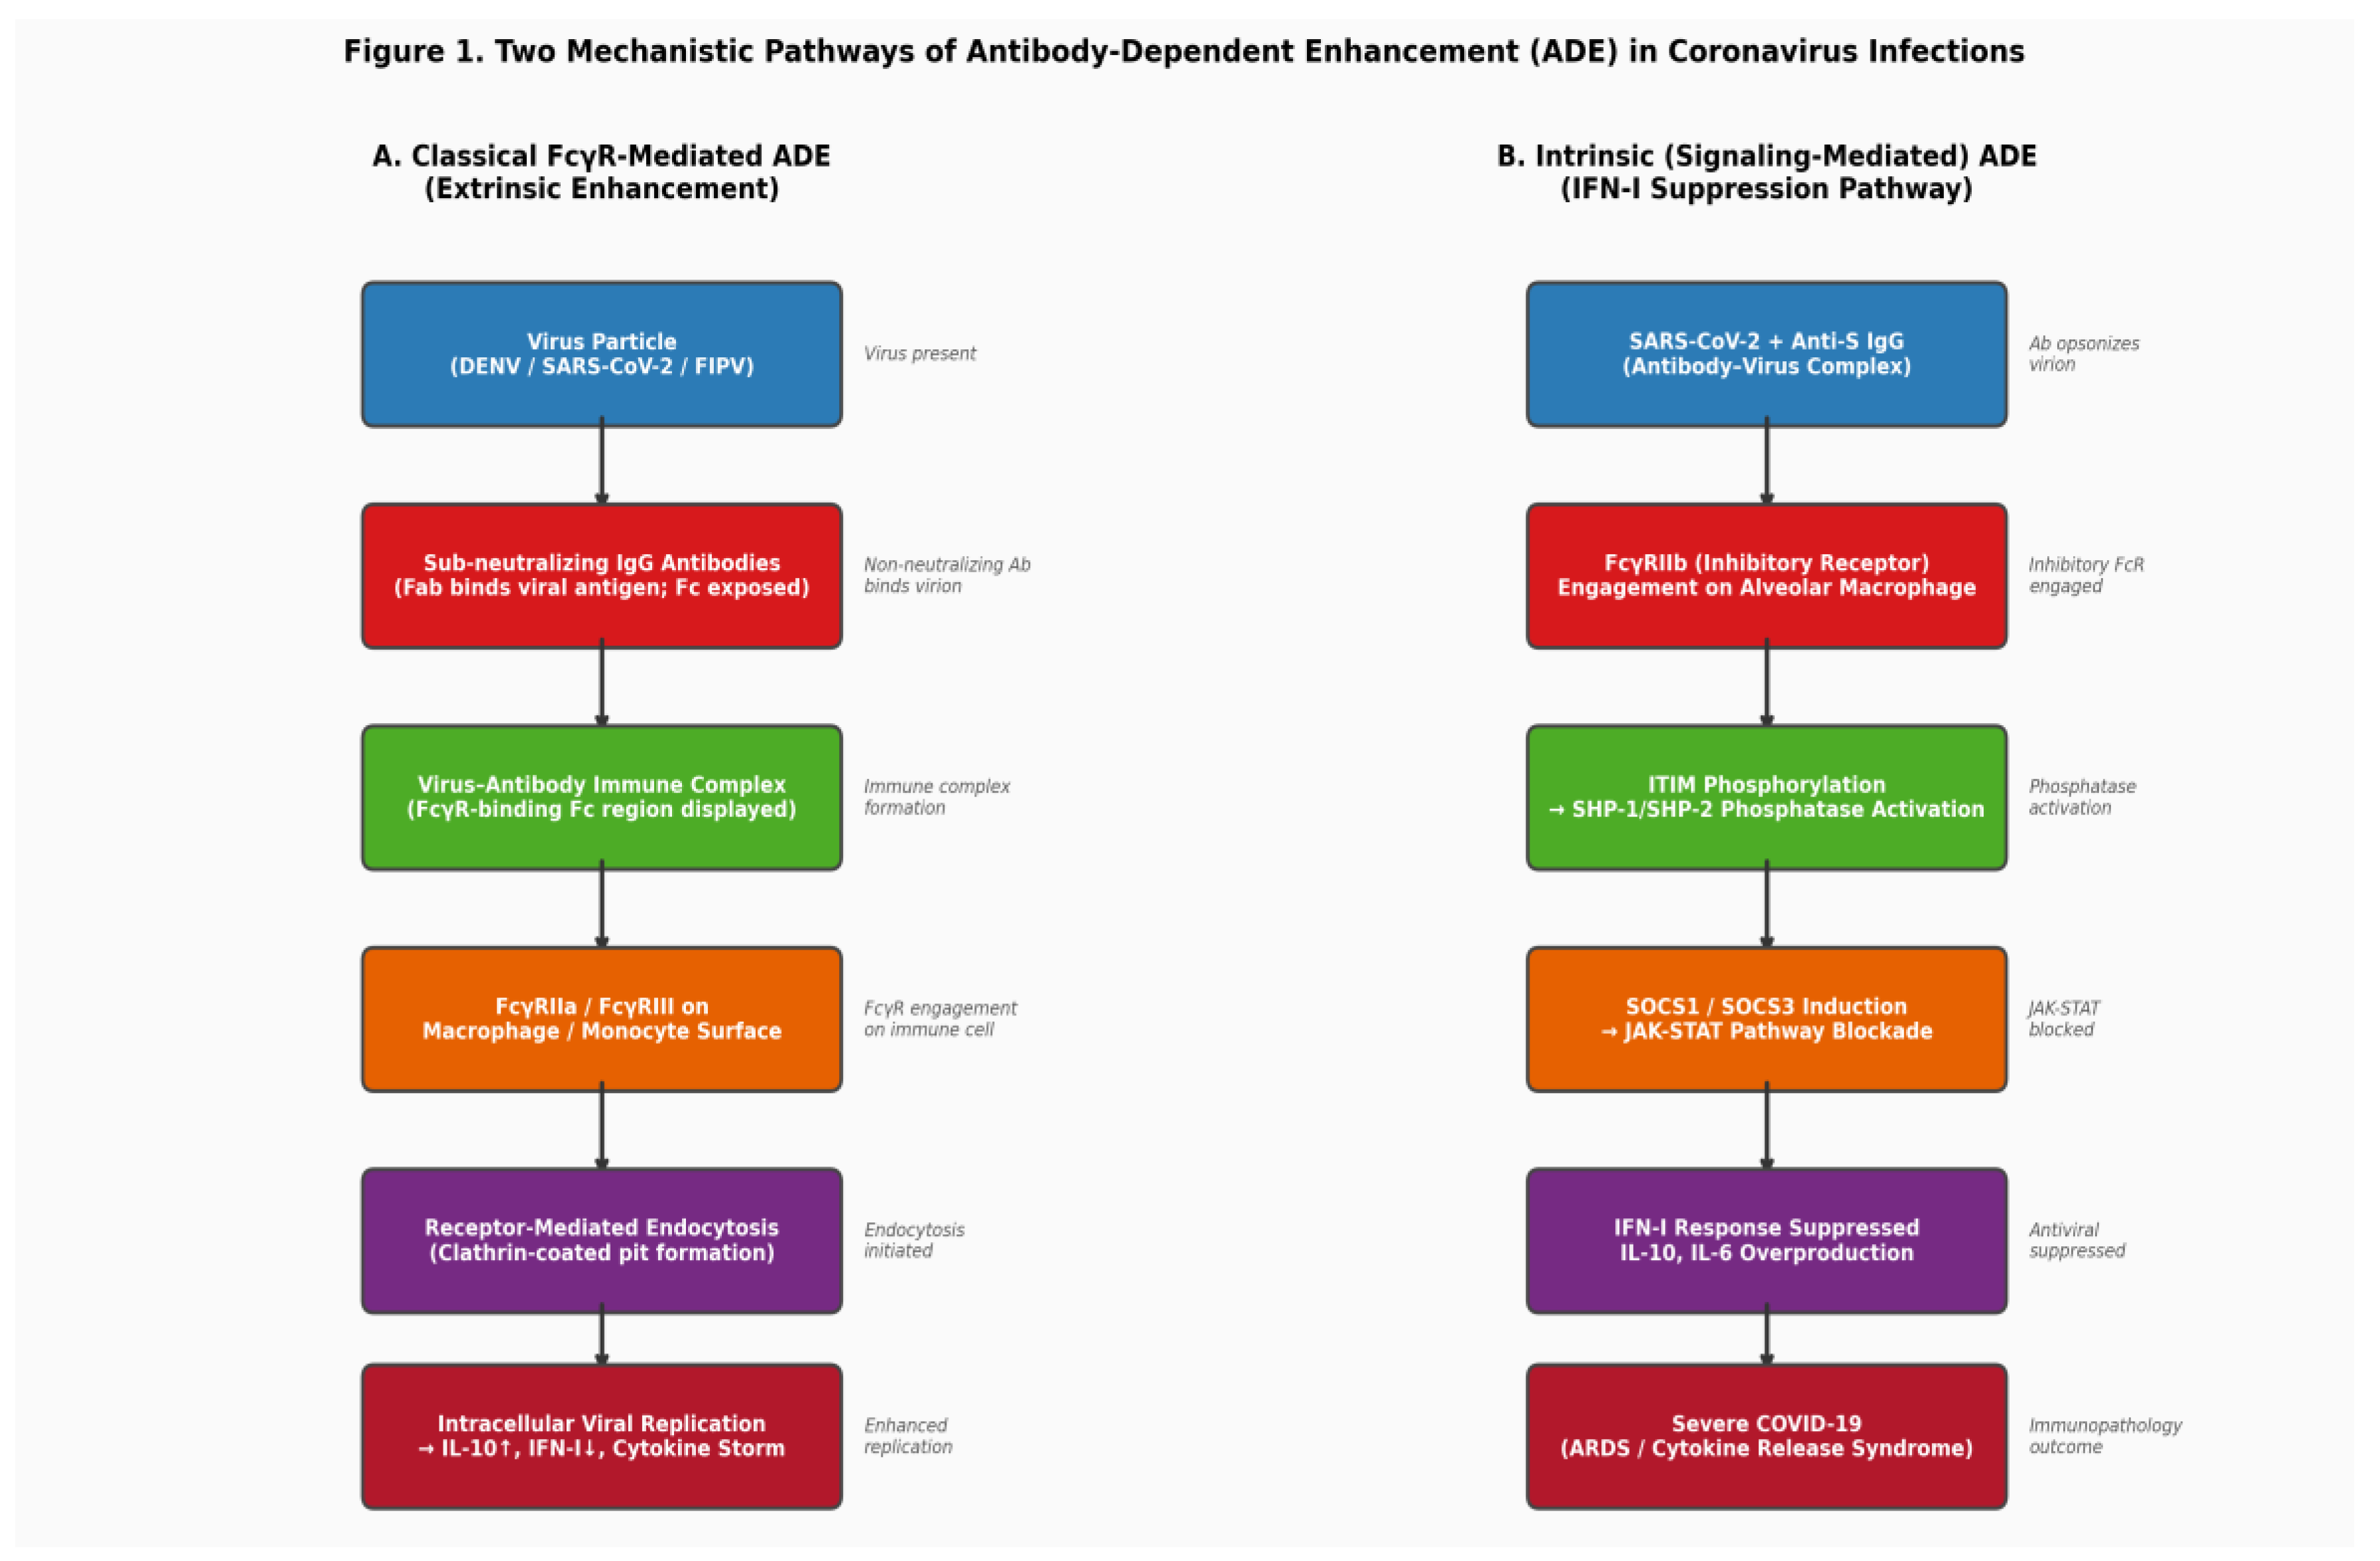
Figure 5.
Intracellular signalling cascade downstream of FcγRIIa engagement during ADE. Syk kinase and PI3K activation diverge into multiple pro-inflammatory and immunosuppressive pathways, culminating in IL-10/IL-6 production, SOCS1/3-mediated IFN-I silencing, and TNF-α/IL-1β release—collectively generating a pro-viral, cytokine-dysregulated macrophage environment characteristic of ADE-mediated coronavirus immunopathology.
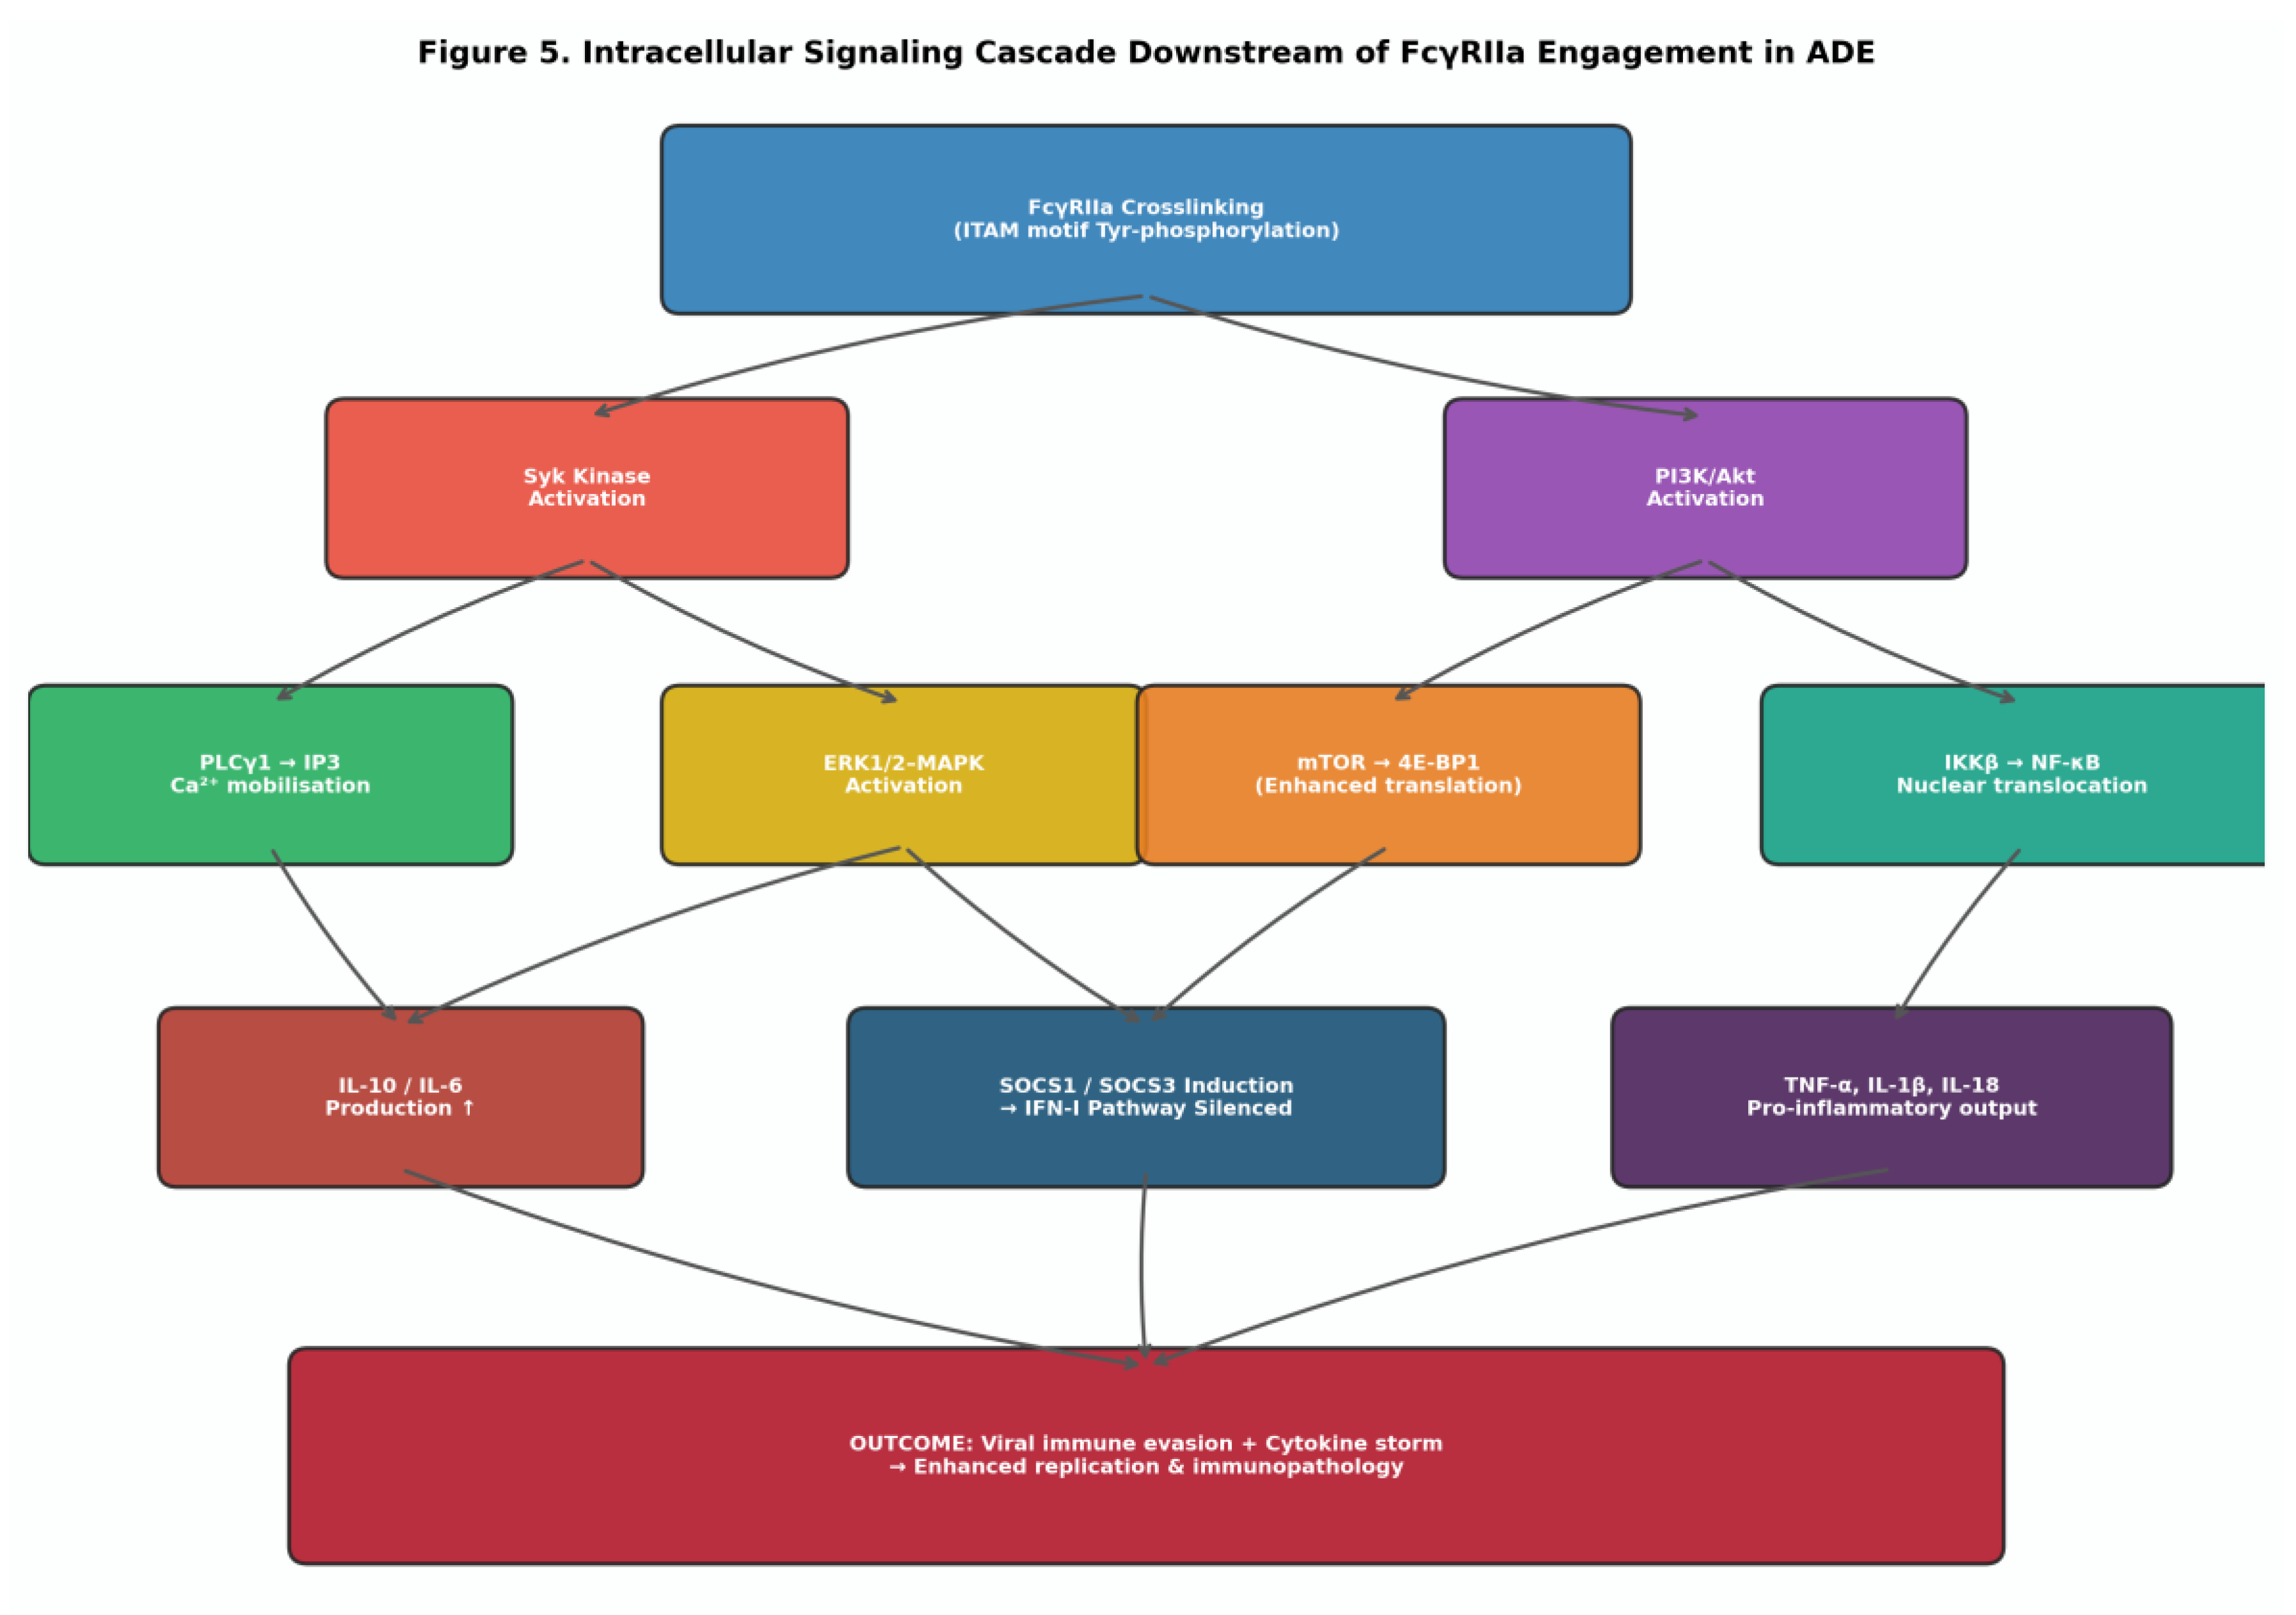
Figure 2.
Proposed cooperative FcγR–ACE2 dual-receptor entry mechanism of SARS-CoV-2 in macrophages/monocytes. The SARS-CoV-2 virion (displaying spike protein with RBD in “up” conformation) simultaneously engages ACE2 via RBD and FcγRIIa via anti-spike IgG Fc. Cooperative dual-receptor engagement stabilises virus–cell contact and enhances endocytosis. Downstream ACE2 (TMPRSS2 activation) and FcγR (ITAM→Syk→PI3K→NF-κB) signals converge, producing IL-10 upregulation and IFN-I suppression that create an intracellular environment permissive for viral replication.
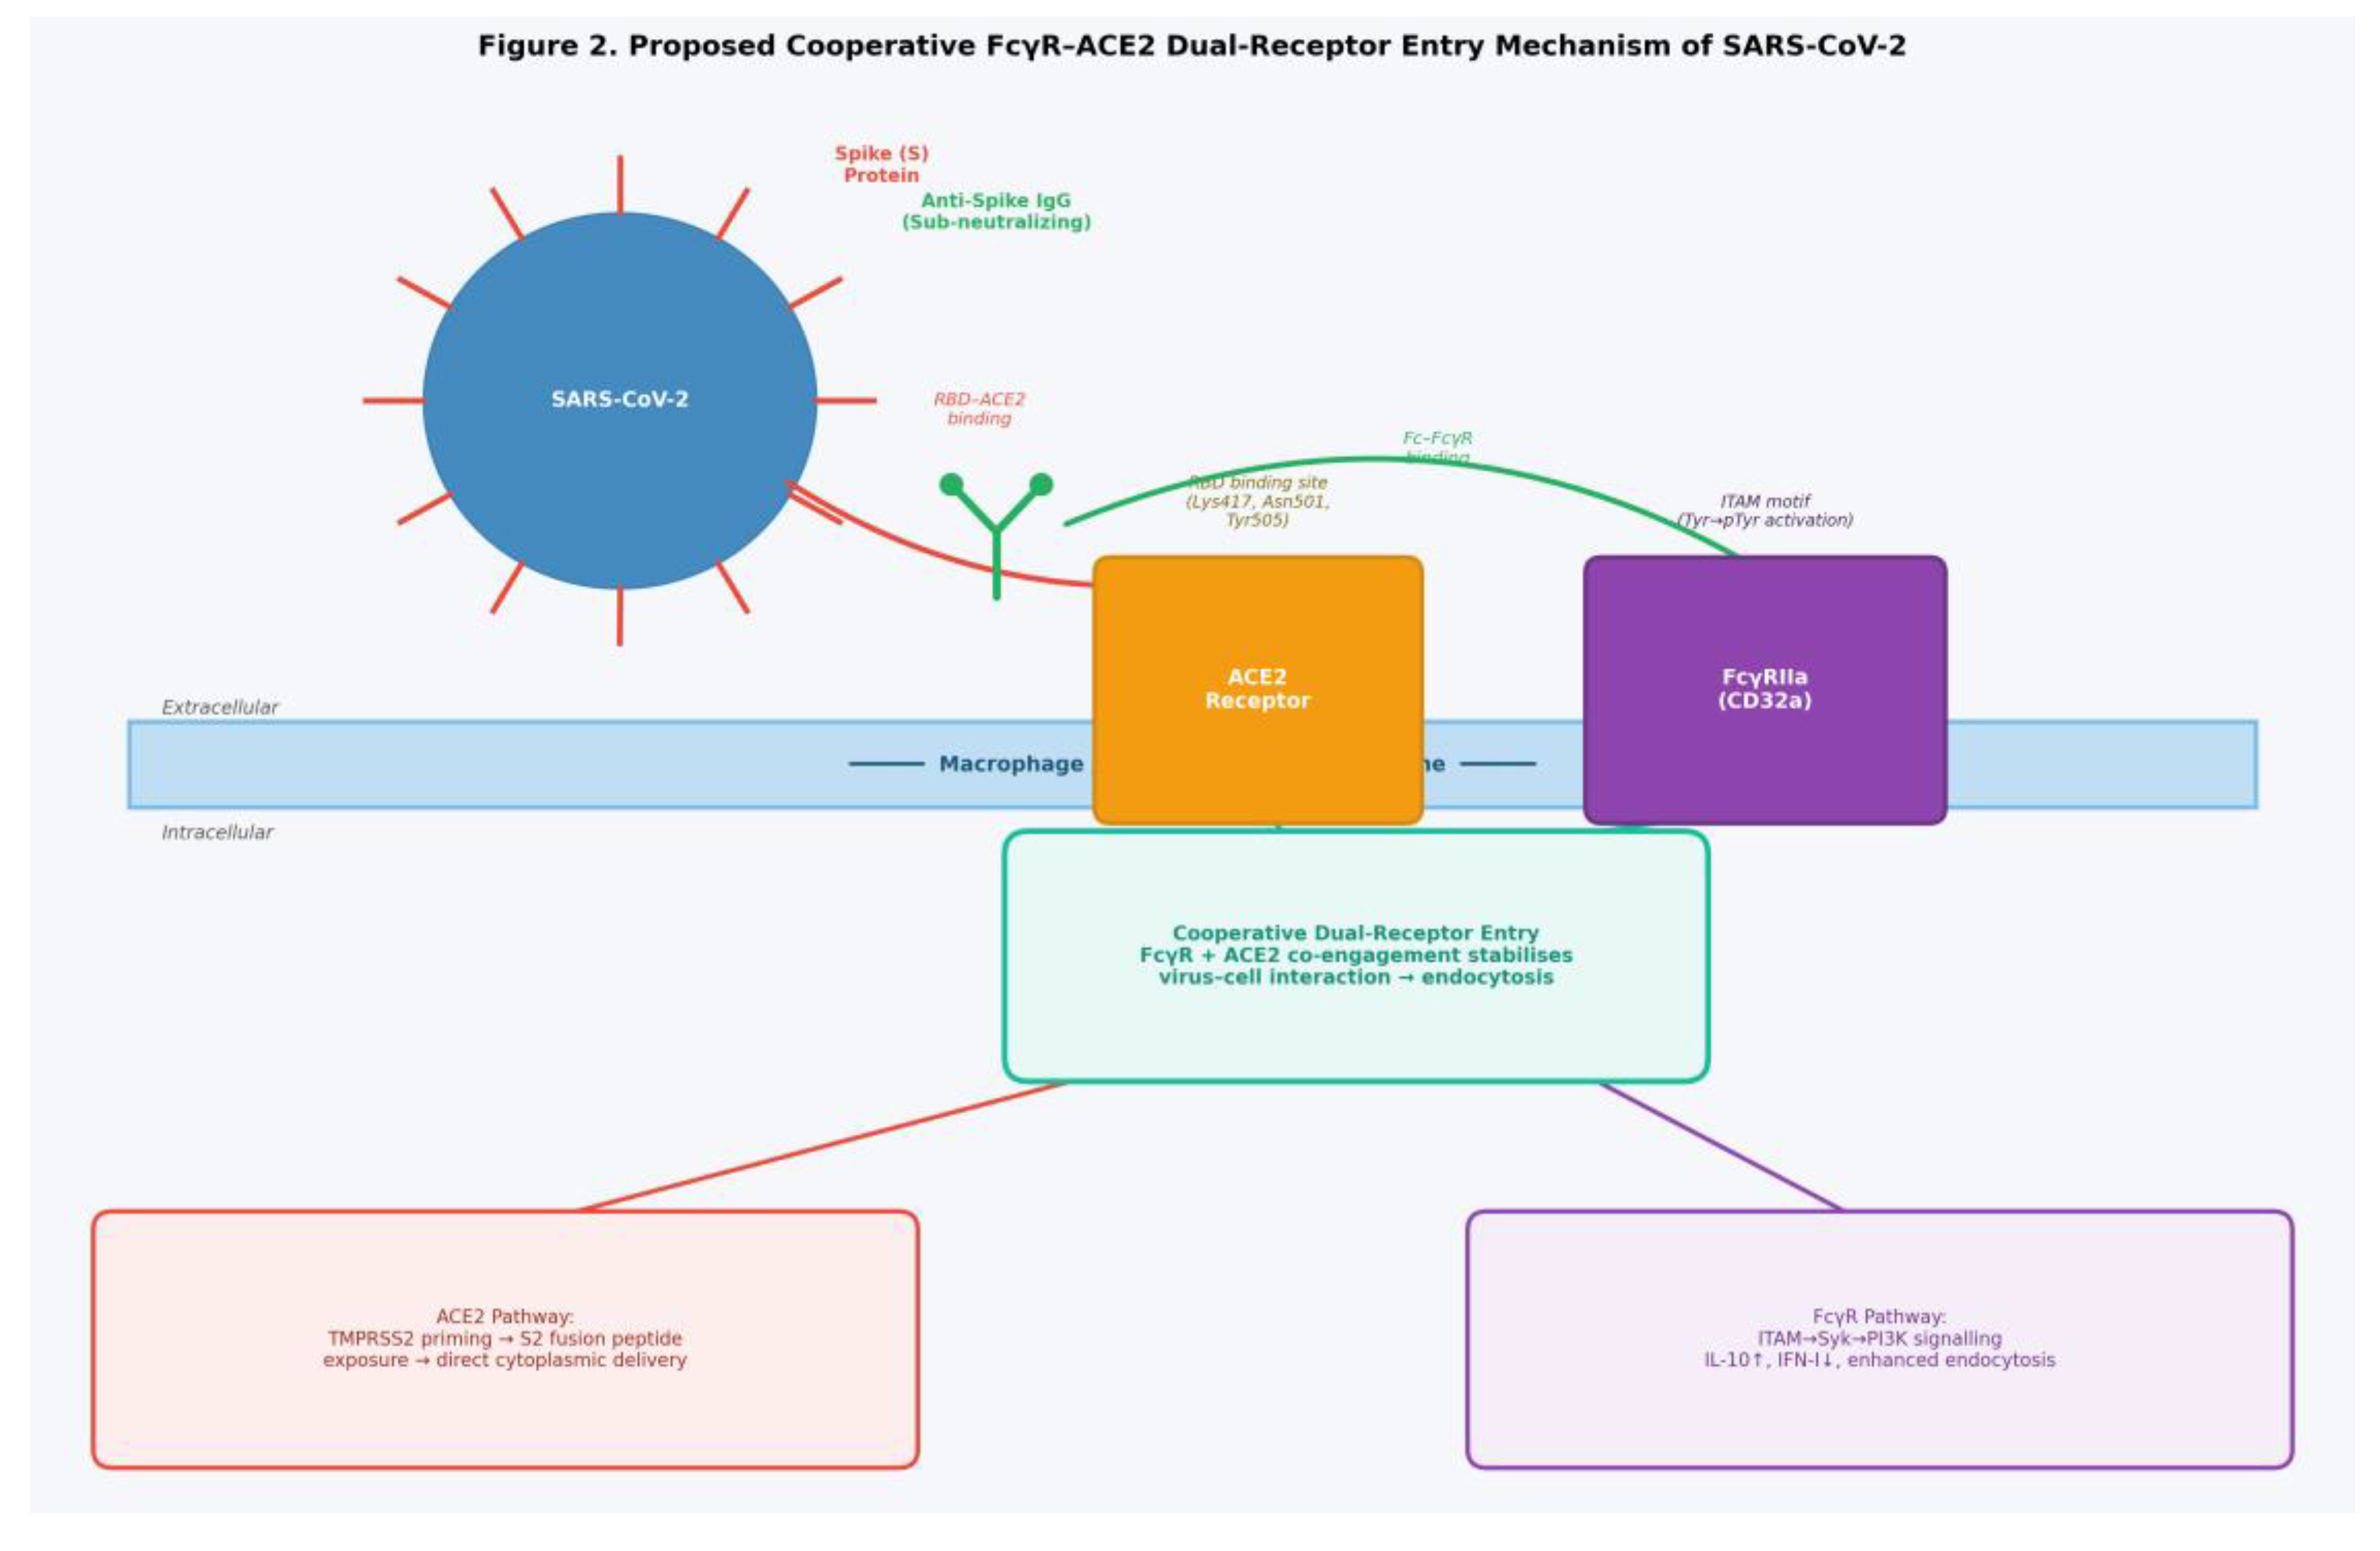
Figure 3.
FIPV ADE pathogenesis: from enteric FCoV mutation to fatal systemic disease. Following FCoV→FIPV spike mutation, non-neutralising anti-FCoV IgG opsonises FIPV, forming immune complexes that are internalised by peritoneal and pleural macrophages via FcγR. Infected macrophages disseminate virus systemically to lymph nodes, liver, spleen, kidney, and CNS, producing pyogranulomatous vasculitis and protein-rich effusions characteristic of fatal wet or dry FIP. ADE is the obligate amplification mechanism enabling this lethal systemic spread.
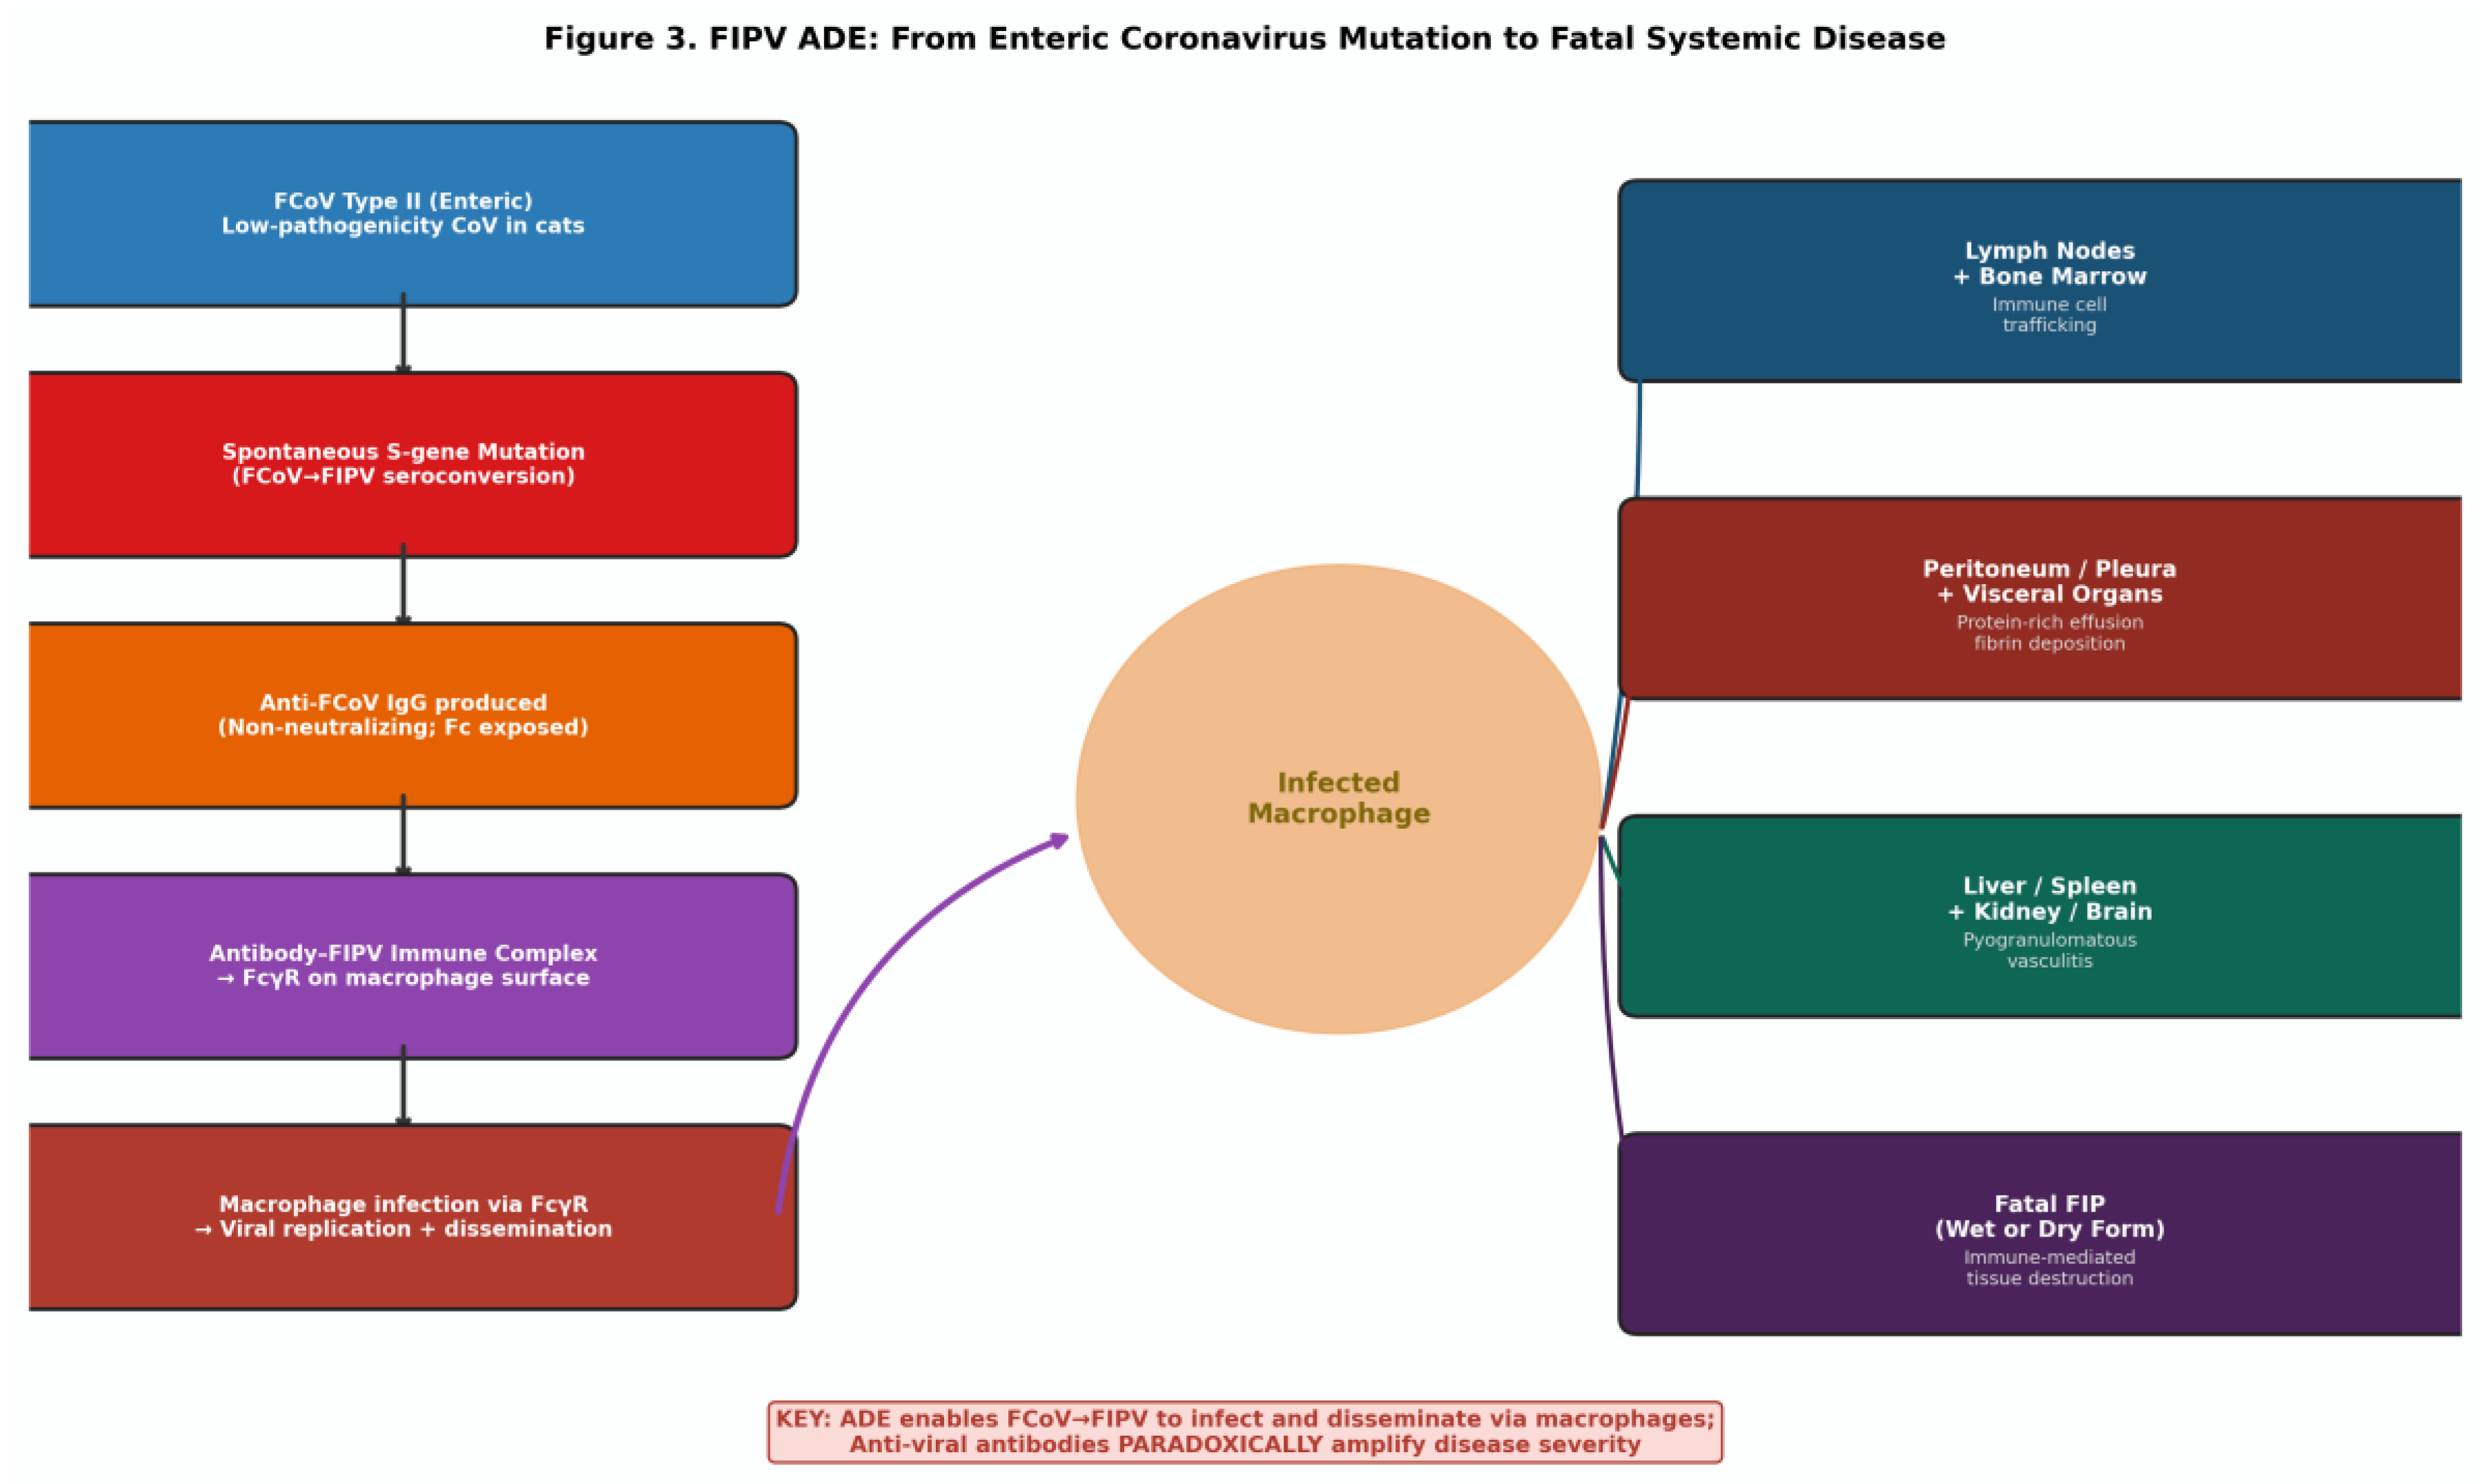
Figure 4.
Nano-engineered vaccine platforms for ADE-safe coronavirus immunisation. Panel A: LNP-mRNA vaccines deliver modified mRNA encoding prefusion-stabilised spike via ionisable lipid endosomal escape; generate core-fucosylated IgG1 nAbs. Panel B: Virus-like particles and nanoparticle-displayed RBD arrays present multivalent neutralising epitopes in geometrically optimised configurations for BCR crosslinking and high-titre nAb induction. Panel C: PLGA/chitosan polymeric nanoparticles provide biodegradable, tunable antigen release with mucosal delivery capability; sIgA induction avoids classical ADE pathway entirely.
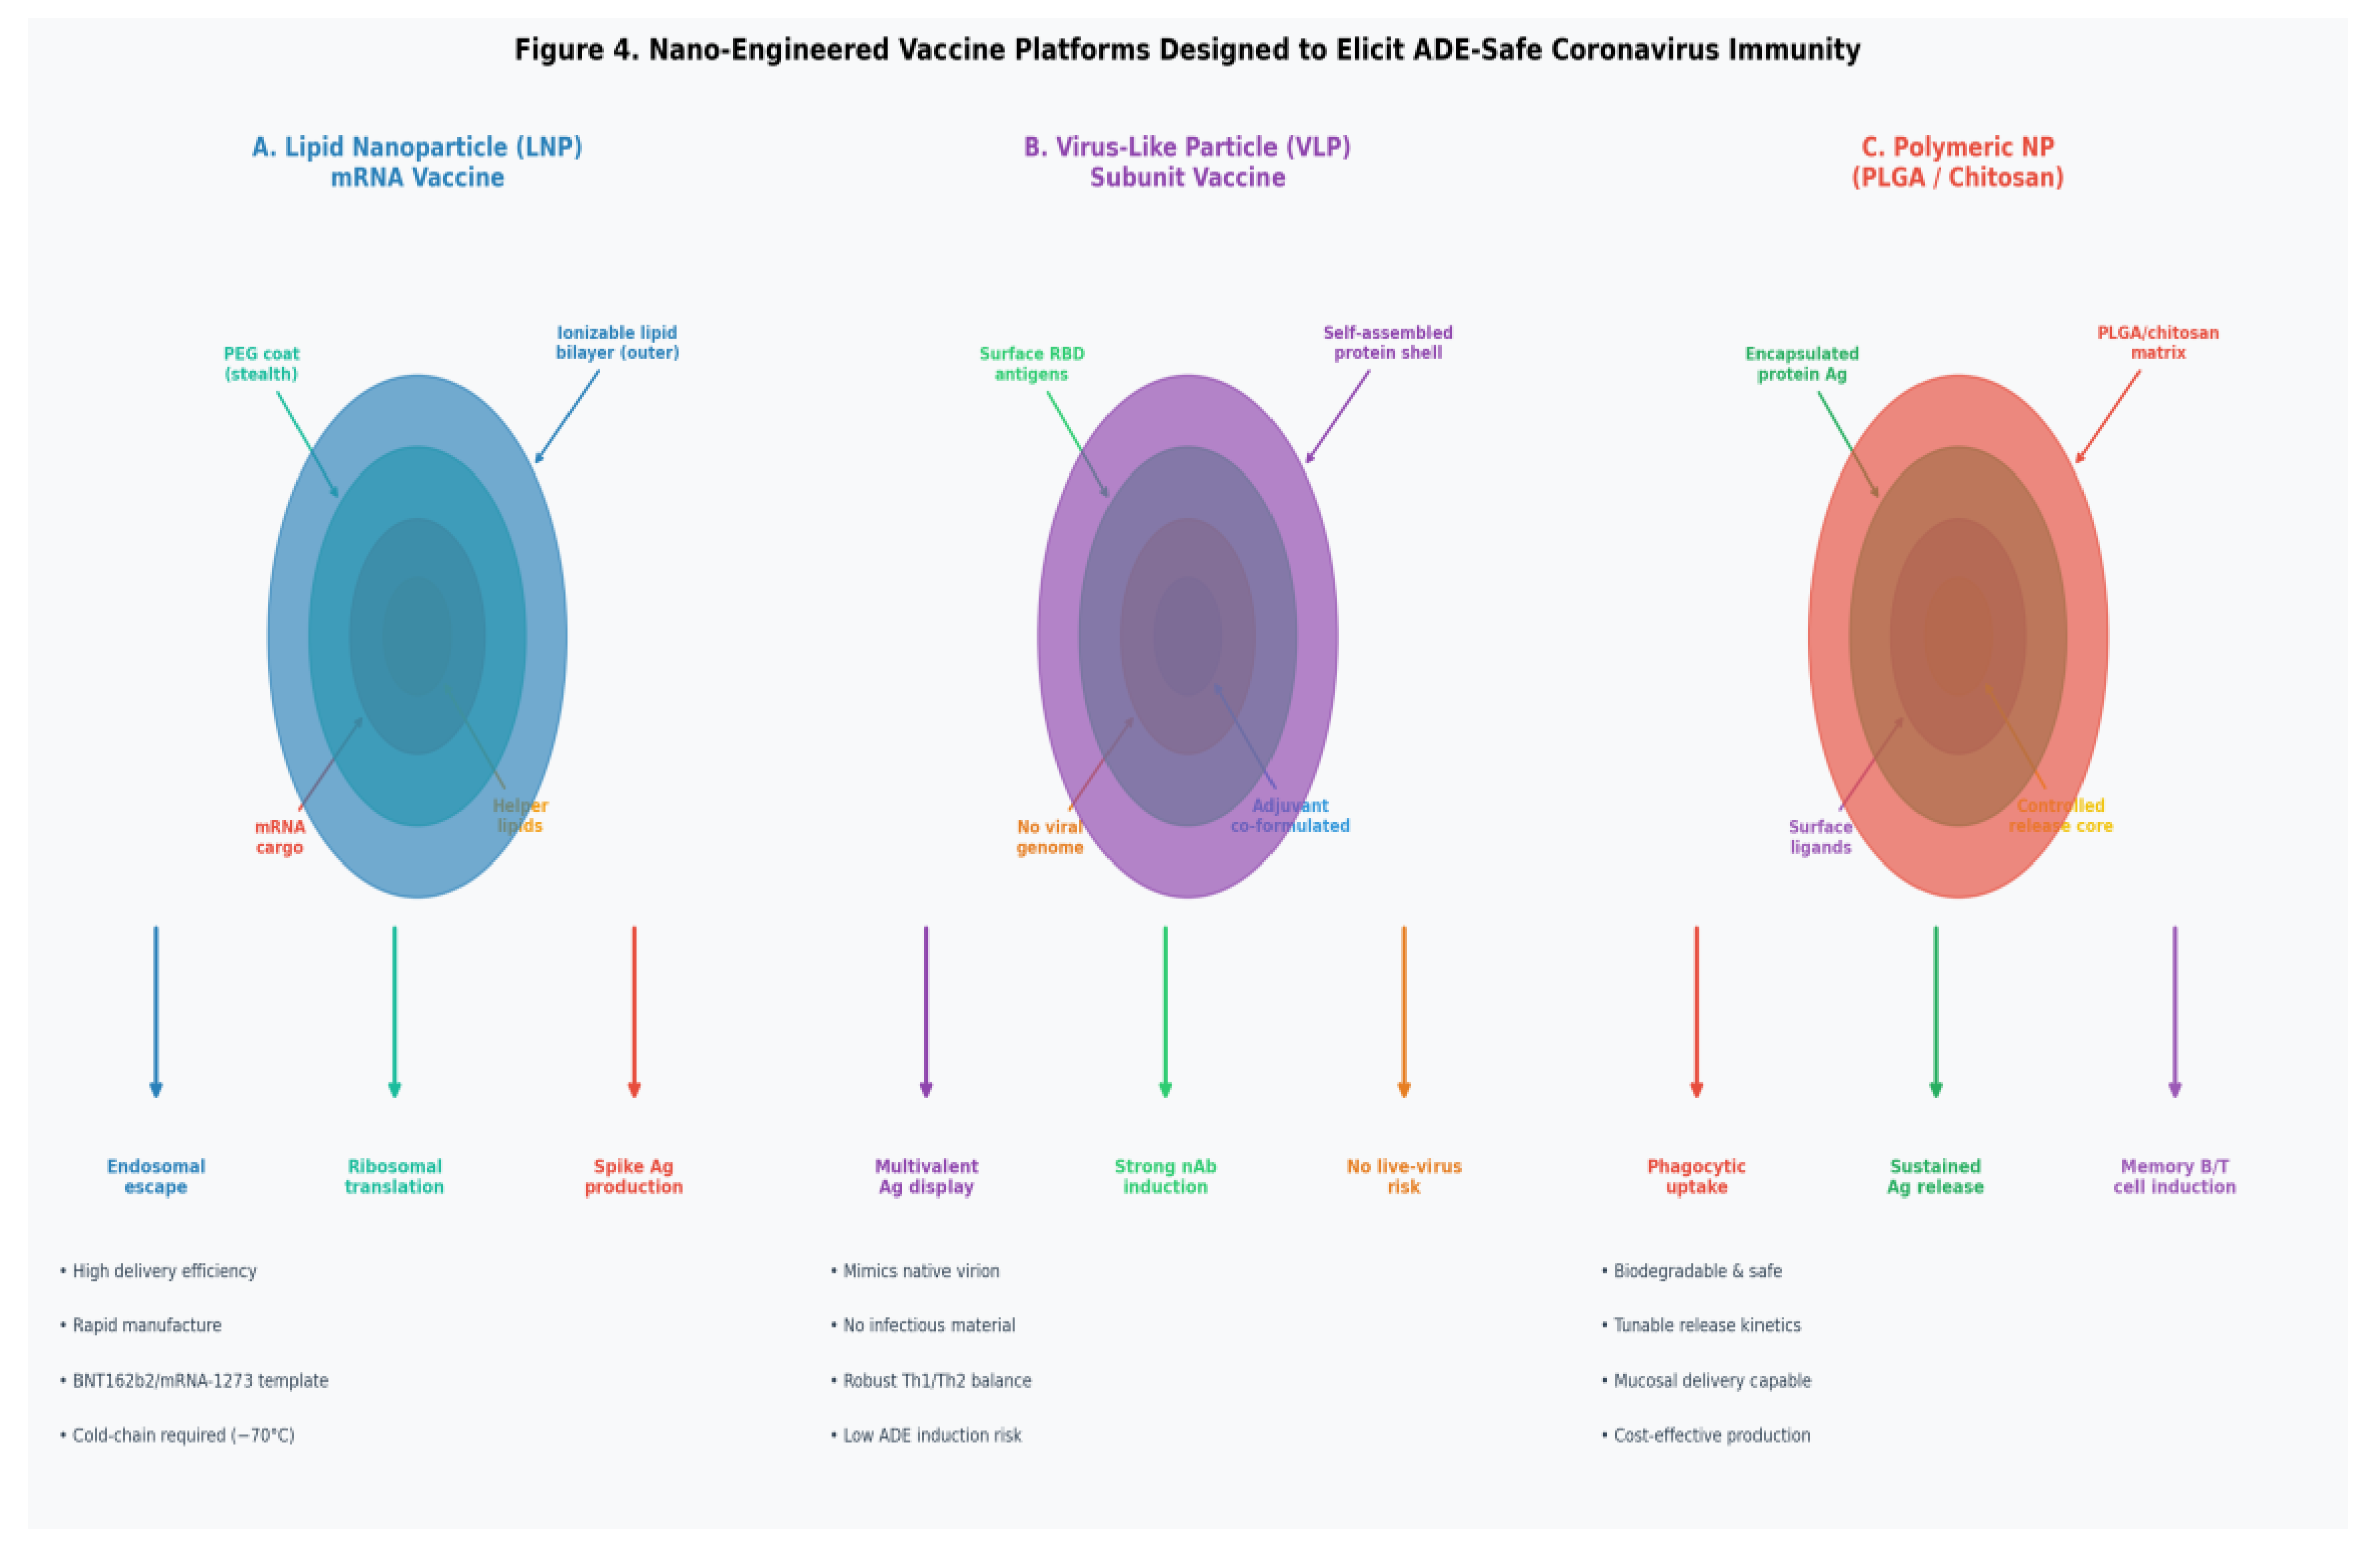

Table 1.
Classification and Properties of Human Fc Gamma Receptors Relevant to ADE.
| FcγR Type | CD Name | IgG Affinity | Cell Expression | Signal Motif | ADE Relevance |
| FcγRI | CD64 | High (Kd ~10−9 M) | Monocytes, Macrophages, DCs | ITAM (γ-chain) | Primary mediator; binds monomeric IgG; high-avidity ADE |
| FcγRIIa | CD32a | Intermediate | Macrophages, Neutrophils, Platelets | ITAM (intrinsic) | Activating; central coronavirus ADE receptor; H131 polymorphism |
| FcγRIIb | CD32b | Intermediate | B cells, Macrophages, DCs | ITIM (inhibitory) | Intrinsic ADE; IFN-I suppression via SHP-1/2; SOCS induction |
| FcγRIIIa | CD16a | Low–Intermediate | NK cells, Macrophages, Monocytes | ITAM (γ/ζ-chain) | ADCC; ADE in monocytes; V158 polymorphism affects affinity |
| FcγRIIIb | CD16b | Low | Neutrophils only | GPI-linked (no signalling) | Phagocytosis; minimal direct ADE role |
Table 1. Classification of human FcγR family members. ITAM, immunoreceptor tyrosine-based activation motif; ITIM, immunoreceptor tyrosine-based inhibitory motif; DCs, dendritic cells.
Table 3.
Comparative Analysis of ADE in SARS-CoV-2 vs FIPV.
| Parameter | SARS-CoV-2 (Human) | FIPV (Feline) |
| Coronavirus lineage | Betacoronavirus (lineage B) | Alphacoronavirus (FCoV type I/II) |
| Primary entry receptor | ACE2 (+ TMPRSS2 co-factor) | APN/CD13; FcγR in ADE |
| ADE mechanism | Extrinsic (FcγRIIa + ACE2 cooperative) + Intrinsic (FcγRIIb-SOCS) | Classical FcγR-mediated macrophage entry; antibody accelerates entry |
| Primary ADE target cell | Alveolar macrophages, monocytes | Peritoneal/pleural macrophages (tissue-resident) |
| Key pathogenic cytokines | IL-6, IL-10, TNF-α; IFN-I suppressed | IL-6, TNF-α, IL-1β; IL-12 reduced |
| Tissue pathology | Diffuse alveolar damage, ARDS | Pyogranulomatous vasculitis, exudative effusions |
| Mortality in severe cases | ~15–40% (critically ill); overall ~1–3% | Near 100% without antiviral therapy |
| Vaccine-enhanced disease | Not observed with mRNA vaccines; theoretical risk exists | Documented with whole-virus and recombinant spike vaccines |
| Therapeutic antiviral | Remdesivir, Paxlovid, molnupiravir | GS-441524 (remdesivir parent compound) |
| Gold-standard ADE model? | Human—limited by ethical constraints on controlled challenge | YES—natural cat model; controlled challenge studies possible |
Table 3. Direct comparison of ADE-relevant parameters between SARS-CoV-2 and FIPV. FIPV provides the most complete natural coronavirus ADE model, with nearly 100% fatal outcome, directly demonstrable antibody-mediated macrophage entry, and documented vaccine-enhanced disease—all directly translatable to coronavirus vaccine safety evaluation.
Table 4.
Comparative Nano-Engineered Vaccine Platform Evaluation for ADE-Safe Coronavirus Vaccination.
Table 4.
Comparative Nano-Engineered Vaccine Platform Evaluation for ADE-Safe Coronavirus Vaccination.
| Platform | Antigen Type | Size Range | Adjuvant? | ADE Risk Mitigation | Stage/Examples |
| LNP-mRNA | Encoded prefusion spike | 80–200 nm | No (self-adj) | Selective nAb1 induction; core-fucosylated IgG Fc; brief Ag expression | Approved: BNT162b2, mRNA-1273 |
| Virus-Like Particle | RBD/spike multimer | 20–100 nm | Often co-formulated | No Fc-activating material; high nAb density; no Fc-triggering genome | HPV/HepB approved; CoV pre-clinical |
| PLGA NP | Protein/peptide subunit | 100–500 nm | MPL, CpG | Sustained release prevents sub-nAb surge window; Th1 bias | Pre-clinical CoV; FDA-approved platforms |
| Chitosan NP | Mucosal protein Ag | 100–600 nm | Intrinsic | Mucosal sIgA induction; sIgA does NOT engage FcγR → no ADE | Pre-clinical; intranasal route |
| Self-assembling NP | Ferritin-RBD, I3-01 scaffold | 10–50 nm | Alum/AS01B | Precise epitope control; avoids immunodominance shift to non-nAb regions | Pre-clinical (HexaPro, SpFN, I53-50) |
Table 4. Comparative evaluation of nano-engineered vaccine platforms. ADE risk mitigation mechanism, antigen type, and clinical/pre-clinical stage are compared across five platform classes. nAb, neutralising antibody; LNP, lipid nanoparticle; PLGA, poly(lactic-co-glycolic acid).
Table 2.
ADE Across Major Pathogenic Viruses: Mechanisms, Target Cells, and Clinical Significance.
| Virus | Family | ADE Mechanism | Target Cell | Key Receptor(s) | Clinical Impact |
| DENV (Dengue) | Flaviviridae | Classical FcγR | Monocytes/Macrophages | FcγRIIa (CD32a) | DHF/DSS; ~25,000 deaths/yr; strongest clinical ADE evidence |
| SARS-CoV-2 | Coronaviridae | Classical + Intrinsic | Alveolar Macrophages, Monocytes | FcγRIIa + ACE2 (cooperative) | COVID-19 cytokine storm; >6M deaths; both pathways implicated |
| SARS-CoV-1 | Coronaviridae | Classical FcγR | Macrophages, DCs | FcγRI, FcγRII | In vitro ADE; vaccine-enhanced disease in animal models |
| FIPV (FCoV) | Coronaviridae | Classical FcγR | Peritoneal Macrophages | Feline FcγR | Fatal FIP; ADE is central, documented, and unavoidable mechanism |
| MERS-CoV | Coronaviridae | Putative Classical | Macrophages, T cells | DPP4 + FcγR (hypothetical) | In vitro evidence; uncertain in vivo significance |
| HIV-1 | Retroviridae | Classical + Complement | CD4+ T cells, Macrophages | FcγRIII, CR3 | Established in vitro; clinical relevance debated |
| Zika Virus | Flaviviridae | Classical FcγR | Placental macrophages, DCs | FcγRIIIa | Congenital Zika risk; cross-reactive DENV Ab implicated |
Table 2. ADE across major viral pathogens. Dengue provides the strongest clinical evidence; SARS-CoV-2 exhibits mechanistic duality (extrinsic + intrinsic ADE); FIPV provides the most controlled natural coronavirus ADE model. DHF, dengue haemorrhagic fever; DSS, dengue shock syndrome; ARDS, acute respiratory distress syndrome; FIP, feline infectious peritonitis.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.