

Submitted:
16 October 2025
Posted:
17 October 2025
You are already at the latest version
Abstract
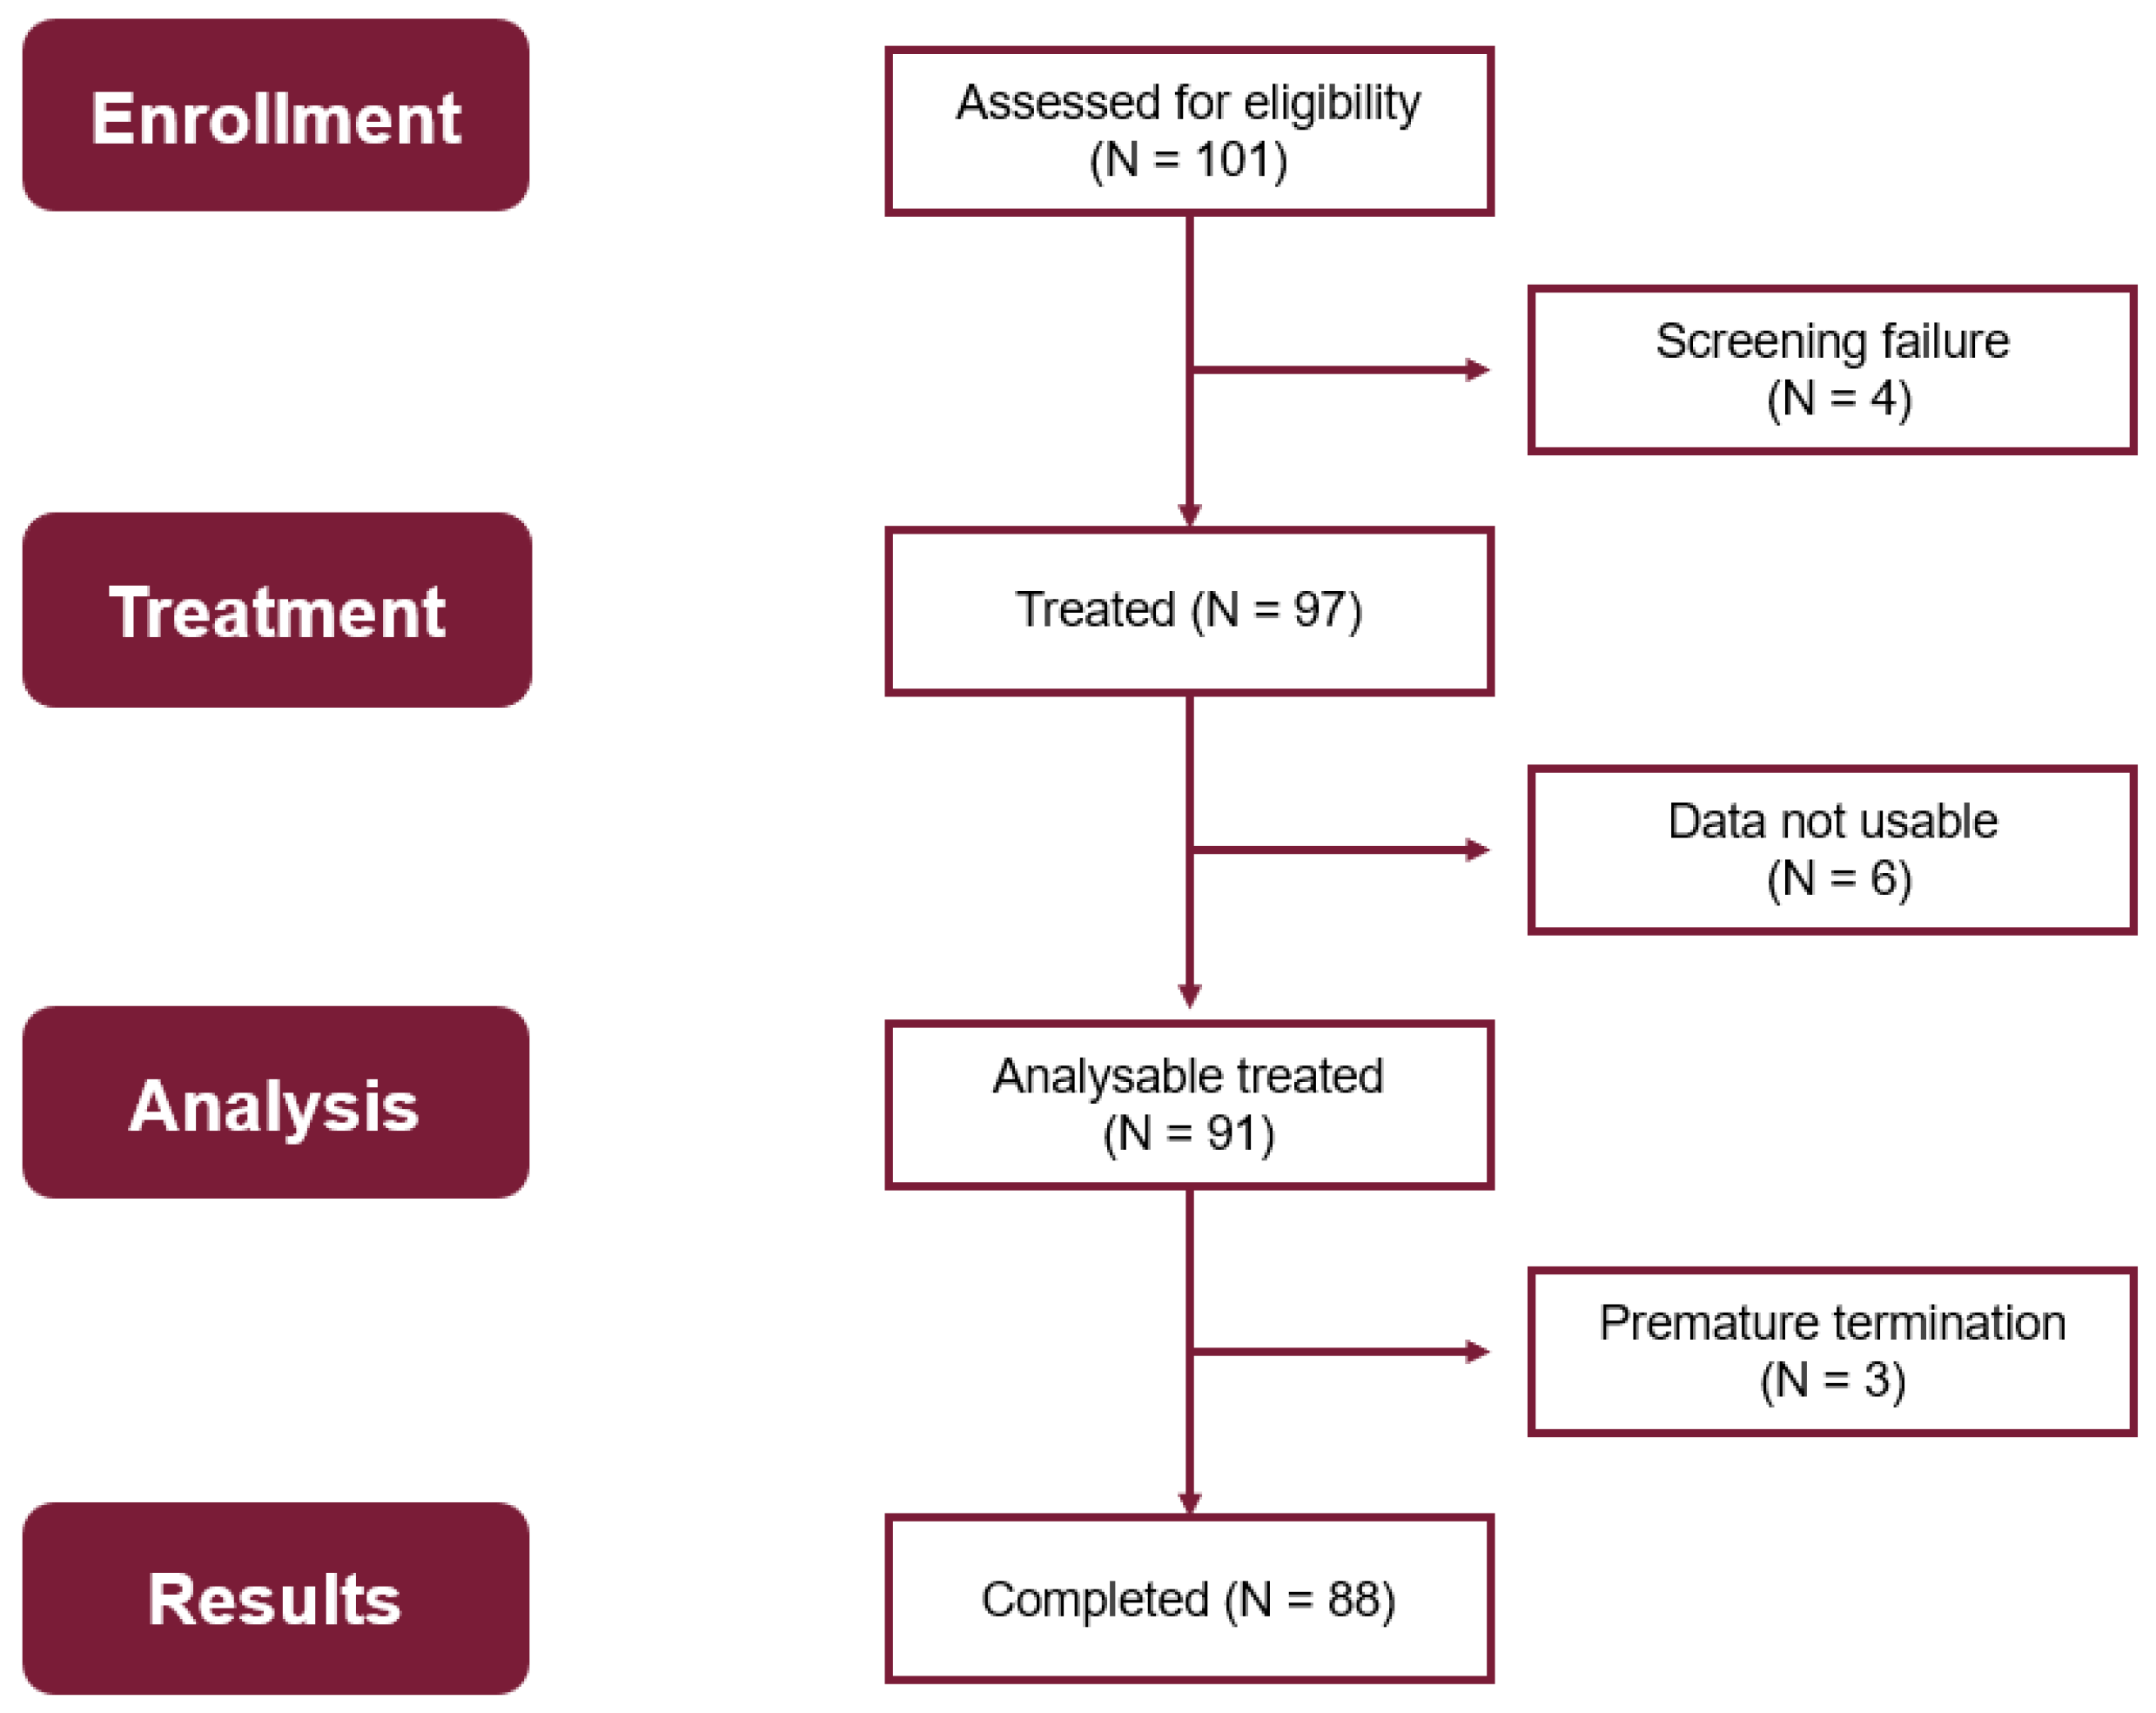
Background/Objectives: For decades, only native allergen extracts with a high incidence of adverse drug reactions (ADRs) were available for allergen-specific immunotherapy (AIT) - in general administered subcutaneously - to treat allergy to feline epithelia. Modified allergen extracts are a promising alternative to reduce the number of ADRs. The purpose of this study was to collect data on the safety of the depigmented allergoid from cat under real-world conditions in clinical routine. Methods: The study was designed as voluntary non-interventional post-authorization safety study (NIS-PASS) with specific focus on the occurrence of adverse events (AEs) – respectively ADRs – upon injections and on the assessment of the influence on quality of life (QoL). Period of observation was the initial phase (up-dosing) of the AIT. Results: 101 patients were included, of whom 91 patients were treated with the depigmented allergoid from cat. Regardless of the age group, around 50% of patients reported ADRs, which were mainly delayed local reactions (LR). Other ADRs occurred only sporadically without persistent impairment for the patients. The incidence of ADRs neither differed significantly between quick and conventional up-dosing regimens nor between adult and adolescent patient groups. The QoL data revealed no significant changes in any domains of the SF-12 questionnaire for the observation period of 12 weeks. Conclusions: Overall, subcutaneous allergen immunotherapy (SCIT) with depigmented allergoid from cat is a well-tolerated and safe treatment option for patients with cat allergy.
Keywords:
1. Introduction
2. Materials and Methods
2.1. Study Design
2.2. Endpoints
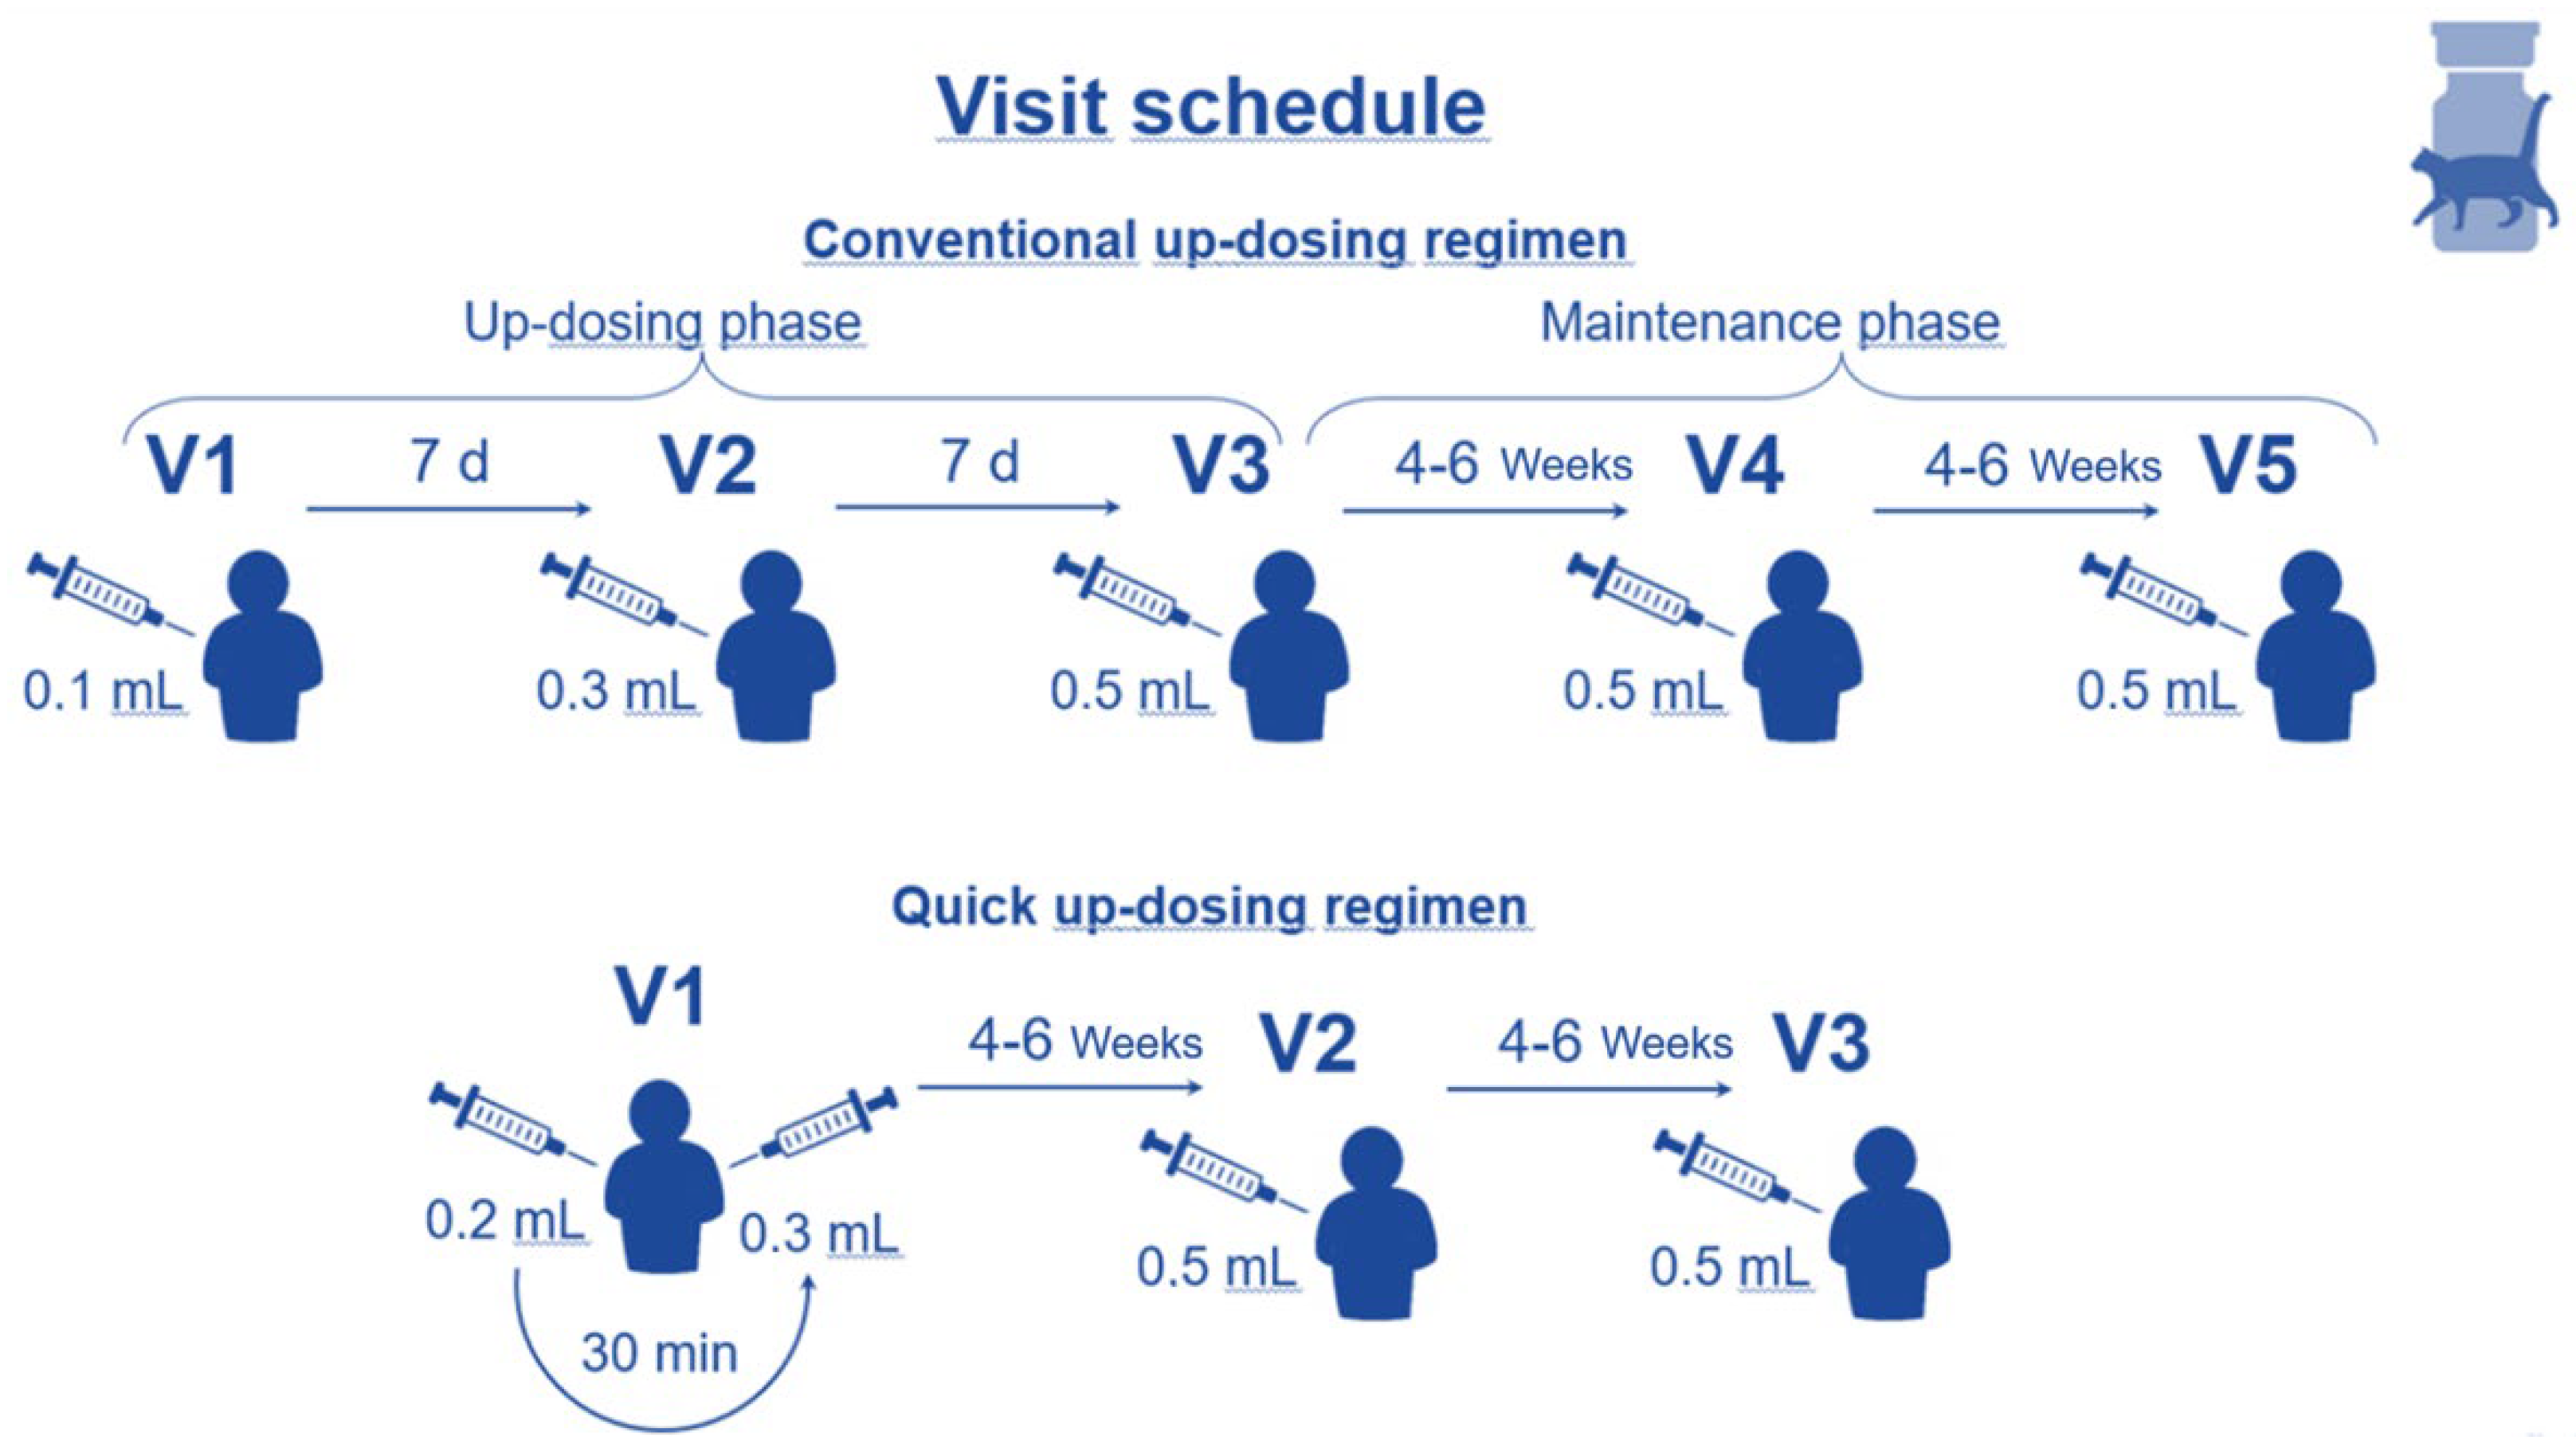
- Comparison of two up-dosing regimens (Conventional Up-dosing Scheme (CUS) versus Quick Up-dosing Scheme (QUS)) regarding the primary variables
- Comparison of CUS and QUS in terms of the proportion of patients reaching the maintenance treatment phase
- Comparison of CUS and QUS regarding the proportion of patients with LR or SR and the level of severity
- Determination of changes in the QoL determined using the SF-12 questionnaire (assessment period: 1 week)
2.3. Setting and Subjects
2.4. Study Flow
2.5. Documentation of Adverse Events (AEs)
- All AEs occurring within 30 minutes after injection as ‘immediate’.
- All AEs occurring >30 minutes after injection as ‘delayed’.
- Local Reactions at the injections site (LR) or
- Systemic Reactions (SR).
2.5. SF-12 Questionnaire
2.6. Data Sources and Management
2.7. Statistical Methods
2.8. Monitoring
2.9. Ethical Supervision
3. Results
4. Discussion
5. Conclusions
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| ADR | Adverse Drug Reaction |
| AE | Adverse Event |
| AIT | Allergen-specific ImmunoTherapy |
| AMG | German Medicines Act (Arzneimittelgesetz) |
| AR | Allergic Rhinitis |
| ARC | Allergic Rhinoconjunctivitis |
| CI | Confidence Interval |
| CRO | Clinical Research Organisation |
| CUS | Conventional Up-dosing Scheme |
| DBPC | Double-Blind Placebo-Controlled |
| EAACI | European Association of Allergy and Clinical Immunology |
| eCRF | Electronic Case Report Form |
| EDC System | Electronic Data Capture System |
| eDiary | Electronic patient Diary |
| ENCePP | European Network of Centres for Pharmacoepidemiology and Pharmacovigilance |
| IgE | Immunoglobulin E |
| ILIT | Intralymphatic ImmunoTherapy |
| LR | Local Reaction |
| MCS | Mental Component Score |
| NIS | Non-Interventional Study |
| OR | Odd’s Ratio |
| p | (p-value) value for significance |
| PASS | Post-Authorisation Safety Study |
| PCS | Physical Component Score |
| P25 | Percentile 25 |
| P75 | Percentile 75 |
| QoL | Quality of Life |
| QUS | Quick Up-dosing Scheme |
| SAE | Serious Adverse Event |
| SAR | Serious Adverse Reaction |
| SCIT | Subcutaneous ImmunoTherapy |
| SF-12 | (Health survey) Short Form 12 questions |
| SLIT | SubLingual ImmunoTherapy |
| SmPC | Summary of Product Characteristics |
| SR | Systemic Reaction |
| V | Visit |
| WAO | World Allergy Organisation |
References
- Sheehan, W., & Phipatanakul, W. (2016, 12 28). Indoor allergen exposure and asthma outcomes. Curr Opin Pediatr., 772-777 . [CrossRef]
- Cacheiro-Llaguno C, Mösges R, Calzada D, González-de la Fuente S, Quintero E, Carnés J. Polysensitisation is associated with more severe symptoms: The reality of patients with allergy. Clin Exp Allergy. 2024 Aug;54(8):607-620. Epub 2024 Apr 27. PMID: 38676405. [CrossRef]
- Simpson, A., & Custovic, A. (2005, May 5). Pets and the development of allergic sensitization. Curr Allergy Asthma Rep, 212-20. [CrossRef]
- Heinzerling LM, Burbach GJ, Edenharter G, et al. GA(2)LEN skin test study I: GA(2)LEN harmonization of skin prick testing: novel sensitization patterns for inhalant allergens in Europe. Allergy. 2009;64(10):1498-1506. [CrossRef]
- van Ree, R., van Leeuwen, W., Bulder, Bond, J., & Aalberse, R. (1999, December). Purified natural and recombinant Fel d 1 and cat albumin in in vitro diagnostics for cat allergy. J Allergy Clin Immunol, 1223-30.
- Charpin, C., Mata, P., Charpin, D., Lavaut, M., Allasia, C., & Vervloet, D. (1991, July). Fel d I allergen distribution in cat fur and skin. J Allergy Clin Immunol, 77-82. [CrossRef]
- Satyaraj E, Sun P, Sherrill S. Fel d1 Blocking Antibodies: A Novel Method to Reduce IgE-Mediated Allergy to Cats. J Immunol Res. 2021 Jun 19;2021:5545173. [CrossRef]
- Alvarez-Cuesta, E., Berges-Gimeno, P., Goncàlez-Mancebo, E., Fernàndez-Caldas, E., Cuesta-Herranz, J., & Casanovas, M. (2007, July). Sublingual immunotherapy with a standardized cat dander extract: evaluation of efficacy in a double-blind placebo-controlled study. Allergy, 810-7. [CrossRef]
- Orengo JM, Radin AR, Kamat V, et al. Treating cat allergy with monoclonal IgG antibodies that bind allergen and prevent IgE engagement. Nat Commun. 2018;9(1):1421. [CrossRef]
- Borchers, A., Keen, C., & Gershwin, M. (2004, October). Fatalities following allergen immunotherapy. Clin Rev Allergy Immunol, 147-58. [CrossRef]
- Nguyen NT, Raskopf E, Shah-Hosseini K, Zadoyan G, Mösges R. A review of allergoid immunotherapy: is cat allergy a suitable target? Immunotherapy. 2016;8(3):331-49. [CrossRef]
- Carnes, Jeronimo, et al. “Allergoids for allergy treatment.” Recent patents on inflammation & allergy drug discovery 12.2 (2018): 110-119. [CrossRef]
- Morales, M., Gallego, M., Iraola, V., Taulés, M., de Oliveira, E., Moya R, R., & Carnés, J. (2017, February 24). In vitro evidence of efficacy and safety of a polymerized cat dander extract for allergen immunotherapy. BMC Immunol. [CrossRef]
- Ibarrola, I., Sanz, M., Gamboa, P., Mir, A., Benahmed, D., Ferrer, A., . . . Asturias, J. (2004, February). Biological characterization of glutaraldehyde-modified Parietaria judaica pollen extracts. Clin Exp Allergy, 303-9. [CrossRef]
- Mösges, R., Santiago , A., Allekotte, S., Jahed, N., Astvatsatourov, A., Sager, A., & Sánchez-López, J. (2019, June 5). Subcutaneous immunotherapy with depigmented-polymerized allergen extracts: a systematic review and meta-analysis. Clin Transl Allergy. [CrossRef]
- Dhami, S., & Agarwal, A. (2018, August). Does evidence support the use of cat allergen immunotherapy? Curr Opin Allergy Clin Immunol., 350-355. [CrossRef]
- Ware J Jr, Kosinski M, Keller SD. A 12-Item Short-Form Health Survey: construction of scales and preliminary tests of reliability and validity. Med Care. 1996 Mar;34(3):220-33.
- Cox, L., Larenas-Linnemann, D., Lockey, R., & Passalacqua, G. (2010, March). Speaking the same language: The World Allergy Organization Subcutaneous Immunotherapy Systemic Reaction Grading System. J Allergy Clin Immunol. [CrossRef]
- Huo, T., Guo, Y., Shenkman, E., & Muller, K. (2018, Feb 13). Assessing the reliability of the short form 12 (SF-12) health survey in adults with mental health conditions: a report from the wellness incentive and navigation (WIN) study. . Health Qual Life Outcomes, 16(1). [CrossRef]
- Pfaar O, Ankermann T, Augustin M, et al. Guideline on allergen immunotherapy in IgE-mediated allergic diseases: S2K Guideline of the German Society of Allergology and Clinical Immunology (DGAKI), Society of Pediatric Allergology and Environmental Medicine (GPA), Medical Association of German Allergologists (AeDA), Austrian Society of Allergology and Immunology (ÖGAI), Swiss Society for Allergology and Immunology (SSAI), German Dermatological Society (DDG), German Society of Oto-Rhino-Laryngology, Head and Neck Surgery (DGHNO-KHC), German Society of Pediatrics and Adolescent Medicine (DGKJ), Society of Pediatric Pulmonology (GPP), German Respiratory Society (DGP), German Professional Association of Otolaryngologists (BVHNO), German Association of Paediatric and Adolescent Care Specialists (BVKJ), Federal Association of Pneumologists, Sleep and Respiratory Physicians (BdP), Professional Association of German Dermatologists (BVDD). Allergol Select. 2022; 6:167-232.
- Zemelka-Wiacek M., Agache I., Akdis C., Akdis M., Casale T., Dramburg S., Jahnz-Różyk K., Kosowska A., Matricardi P., Pfaar O., Shamji M., Jutel M. (2024, April). Hot topics in allergen immunotherapy, 2023: Current status and future perspective. J Allergy Clin Immunol. 830-831. [CrossRef]
- Lilja G., Sundin B., Graff-Lonnevig V., Hedlin G., Heilborn H., Norrlind K., Pegelow K.O., Løwenstein H. (1989, March). Immunotherapy with cat- and dog-dander extracts. IV. Effects of 2 years of treatment. J Allergy Clin Immunol. 42-44.
- Vázquez de la Torre M, López-González P, Haroun-Díaz E, Somoza ML, Cervera MD, Ruiz-García M, Ruano FJ. Depigmented, Polymerized Cat Epithelium Extract Is Safe and Improves Rhinitis and Asthma Symptoms in Cat-Allergic Patients: A Real-World Retrospective Study. Int Arch Allergy Immunol. 2025;186(6):532-542. [CrossRef]

| Severity of LR | Diameter of wheal/redness (of LR) |
| Mild | >0 to ≤5 cm |
| Moderate | >5 to ≤10 cm |
| Severe | >10 cm |
| Presence of at least one AE | ||||
| No n (%) | Yes n (%) | Total n (%) | ||
| Adolescents | CUS* | 1 (20%) | 4 (80%) | 5 (56%) |
| QUS* | 3 (75%) | 1 (25%) | 4 (44%) | |
| Total | 4 (44%) | 5 (56%) | 9 (100%) | |
| Adults | CUS | 22 (43%) | 29 (57%) | 51 (62%) |
| QUS | 16 (52%) | 15 (48%) | 31 (38%) | |
| Total | 38 (46%) | 44 (54%) | 82 (100%) | |
| Total | CUS | 23 (41%) | 33 (59%) | 56 (62%) |
| QUS | 19 (54%) | 16 (46%) | 35 (38%) | |
| Total | 42 (46%) | 49 (54%) | 91 (100%) | |
| p-value | p=0.914** | |||
| * CUS = conventional up-dosing scheme / QUS = quick up-dosing scheme **Chi-Square test comparing incidence of AEs in adolescents with adults | ||||
|
Severity of immediate LR No. and % of patients (n (%) |
Severity of delayed LR No. and % of patients (n (%) |
|||||||||
| Mild | Moderate | Severe | Total | Mild | Moderate | Severe | Total | |||
| Adolescents CUS* | 0 (0%) | 0 (0%) | 0 (0%) | 0 0(0%) | 2 (67%) | 1 (33%) | 0 (0%) | 3 (75%) | ||
| QUS* | 1 (100%) | 0 (0%) | 0 (0%) | 1 (100%) | 0 (0%) | 0 (0%) | 1 (100%) | 1 (25%) | ||
| Total | 1 (100%) | 0 (0%) | 0 (0%) | 1 (100%) | 2 (50%) | 1 (25%) | 1 (25%) | 4 (100%) | ||
|
Adults CUS |
8 (67%) | 4 (33%) | 0 (0%) | 12 (60%) | 17 (71%) | 5 (21%) | 2 (8%) | 24 (67%) | ||
| QUS | 3 (38%) | 4 (50%) | 1 (13%) | 8 (40%) | 11 (92%) | 1 (8%) | 0 (0%) | 12 (33%) | ||
| Total | 11 (55%) | 8 (40%) | 1 (5%) | 20 (100%) | 28 (78%) | 6 (17%) | 2 (6%) | 36 (100%) | ||
|
Total CUS |
8 (67%) | 4 (33%) | 0 (0%) | 12 (57%) | 19 (70%) | 6 (22%) | 2 (7%) | 27 (68%) | ||
| QUS | 4 (44%) | 4 (44%) | 1 (11%) | 9 (43%) | 11 (85%) | 1 (8%) | 1 (8%) | 13 (33%) | ||
| Total | 12 (57%) | 8 (38%) | 1 (5%) | 21 (100%) | 30 (75%) | 7 (18%) | 3 (8%) | 40 (100%) | ||
| p-value | p = 0.394** | p = 0.190** | ||||||||
| * CUS = conventional up-dosing scheme / QUS = quick up-dosing scheme **Chi-Square test comparing incidence of AEs in adolescents with adults | ||||||||||
|
Grade of immediate SR No. and % of patients (n (%) |
Grade of delayed SR No. and % of patients (n (%) |
|||||
| Grade 1 | Grade 2 | Total | Grade 1 | Grade 2 | Total | |
| Adolescents CUS | 0 (0%) | 0 (0%) | 0 (0%) | 0 (0%) | 1 (100%) | 1 (100%) |
| QUS | 0 (0%) | 0 (0%) | 0 (0%) | 0 (0%) | 0 (0%) | 0 (0%) |
| Total | 0 (0%) | 0 (0%) | 0 (0%) | 0 (0%) | 1 (100%) | 1 (100%) |
|
Adults CUS |
1 (25%) | 3 (75%) | 4 (50%) | 7 (58%) | 5 (42%) | 12 (75%) |
| QUS | 0 (0%) | 4 (100%) | 4 (50%) | 2 (50%) | 2 (50%) | 4 (25%) |
| Total | 1 (13%) | 7 (88%) | 8 (100%) | 9 (56%) | 7 (44%) | 16 (100%) |
|
Total CUS |
1 (25%) | 3 (75%) | 4 (50%) | 7 (54%) | 6 (46%) | 13 (76%) |
| QUS | 0 (0%) | 4 (100%) | 4 (50%) | 2 (50%) | 2 (50%) | 4 (24%) |
| Total | 1 (13%) | 7 (88%) | 8 (100%) | 9 (53%) | 8 (47%) | 17 (100%) |
| p-value | - | p = 0.289* | ||||
| CUS = conventional up-dosing scheme / QUS = quick up-dosing scheme *Mann Whitney U test comparing incidence of SRs in adolescents with adults | ||||||
| Difference of PCS12* | Difference of MCS12* | ||||||||
| Valid N | P25** | Median | P75** | Valid N | P25** | Median | P75** | ||
| Adolescents | CUS | 4 | -1.27 | -0.41 | 1.06 | 4 | -4.35 | 0.29 | 5.53 |
| QUS | 4 | -4.97 | -2.65 | -1.75 | 4 | 4.46 | 7.77 | 12.73 | |
| Total | 8 | -2.65 | -1.51 | -0.41 | 8 | -0.25 | 5.00 | 8.31 | |
| Adults | CUS | 50 | -2.13 | 0.04 | 1.70 | 50 | -2.68 | 0.14 | 2.48 |
| QUS | 28 | -2.87 | -0.65 | 2.51 | 28 | -3.12 | -0.79 | 2.55 | |
| Total | 78 | -2.57 | 0.00 | 2.49 | 78 | -3.01 | 0.00 | 2.48 | |
| Total | CUS | 54 | -1.96 | 0.00 | 1.70 | 54 | -3.09 | 0.14 | 2.67 |
| QUS | 32 | -2.91 | -0.94 | 2.10 | 32 | -2.54 | -0.05 | 4.27 | |
| Total | 86 | -2.57 | -0.11 | 1.71 | 86 | -3.01 | 0.00 | 3.23 | |
| * Physical component score (PCS), mental component score (MCS) / ** Percentile 25 / Percentile 75 / CUS = conventional up-dosing scheme / QUS = quick up-dosing scheme | |||||||||
| Physical health (PCS) | Mental health (MCS) | |||
| Up-dosing scheme (no of patients) | CUS n=4 |
QUS n=4 |
CUS n=4 |
QUS n=4 |
| Baseline | 42.9±1.4 | 44.4±1.9 | 42.8±4.9 | 39.9±1.7 |
| End of observation period | 42.8±1.5 | 41.0±2.3 | 43.4±6.2 | 48.5±3.7 |
| CUS = conventional up-dosing scheme / QUS = quick up-dosing scheme | ||||
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).