

Submitted:
11 September 2025
Posted:
12 September 2025
You are already at the latest version
Abstract
Purpose: This paper aims to examine the empirical studies and scholarly articles on child marriages and mental health implications for young female adults in Africa. Methodology : A systematic literature review was conducted to understand child marriage and the construction of mental health implications for young female adults in Africa. The authors did a comprehensive search of electronic databases using relevant key terms. Findings: The review revealed that mental health and child marriage are under-researched in Africa. The majority of the studies on child marriages were centred on the impact, factors causing child marriage, and human and children’s rights being violated as a result of child marriage. This paper aims to fill in the gap in the literature on child marriage and mental health. Practical implications: Captivating propositions which could be used as a reference to understand child marriage and mental health implications for young female adults in Africa were proposed.
Keywords:
Africa
; child marriage
; mental health
; young female adults
1. Introduction
Child marriage experience is mentally draining for young female adults who are not psycho-socially prepared for marriage (Burgess, 2022; John et al, 2019). Evidence suggests that marriage below the age of consent leads to mental breakdown (Fan and Koski, 2022). Psychologists have further emphasized that mental health conditions emanate during adolescence, where one in every six individuals at the age of 10-19 years suffer from mental health disorders (Kessler et al., 2007). The lived experiences of young female adults in child marriages usually below the age of 16 or 18 years, depending on the country. have been discussed in the literature as vulnerability and risk to mental health problems (Ahmed et al., 2013, Atiola, 2014; Gore et al., 2011; Groot et.al., 2018 Kidman, 2017).
The objective of this systematic review is to shed light on the constructions of mental health implications because of child marriages, to inform intervention programs and policies, and provide critical areas needing future research.
The present study contributes to the literature by focusing on mental health and child marriage in Africa. In contrast to the Global South, the Global North has discussed more on young female adults' mental health and child marriage (Laurenzi et al., 2020; Barnet et al., 2002). Researchers in the Global South have just recently begun to examine the mental health of young women who are in child marriages. Few studies have looked at the mental health of young women who are HIV/AIDS positive and living in Africa (Roberts et al., 2021; Boyes et al., 2019; Cluver et al., 2022; West et al., 2019 & Woollett et al., 2017). Studies on mental health and child marriage are thus under-researched.
The focus and budget allocations towards HIV/AIDS, tuberculosis, childhood vaccination, and malaria in the African continent are overwhelming. Mental health, neurological, and substance abuse disorders are significantly ignored in the African continent (Lund, 2011). Yet, in Africa, mental health dominates a bigger percentage of the burden of ailments, only 1% of the national health budget is given to mental health (WHO, 2005). The allocated budget covers the colonial age safeguarding psychiatric institutes, contrary to rising data for cost-effective community-based interventions (Patel et al., 2007). To shed light on this under-researched topic, we conducted a systematic literature review to identify gaps and suggest areas for future research and policy guidelines.
2. Methodology
The systematic literature review identifies, selects, and critically appraises research to answer a formulated question (Dewey and Drahota, 2016). The method suits the aim of the study, which is to examine the empirical studies and scholarly articles on the topic of child marriage and the construction of mental health implications for young female adults in Africa.
In this paper, we present the impact of child marriage on the mental health of young female adults exposed to early marriages. To comprehend the topic, we applied a systematic literature review. The following research question guided our study:
- What is the impact of child marriage on young female adults’ mental health and well-being in Africa?
The paper is organised as follows, the first section, presents the introduction of the study. Subsequent sections discuss the methodology, results, discussion of our systematic literature review, recommendations, and conclusion, and insights for future studies.
This paper applied a systematic literature review search to detect the types and motivational factors of child marriages and mental health implications on young female adults in Africa. A systematic literature review was crucial because it offered a thorough and complete summary of the current studies and upheld the development of innovative theories (Webster & Watson, 2002). The advantage of applying a systematic literature review is that it improves the transparency in methodology and makes it better to reproduce the results guided by predefined search strategies (Denyer & Transfield, 2009).
The systematic literature review has three main aspects that the researchers implemented; planning, conducting the review, and reporting, followed by other steps including identification of the resources, selection of the study, and data extraction (Kitchenham, 2004). We started with the planning of how to conduct the overall study; then, worked on the identification of the relevant studies that can answer the research question.
To have suitable data, we followed the procedures drawn by Tranfield et al. (2003). The researchers. We conducted an electronic search; with key terms that were found in scholarly articles including ‘mental health’, ‘young female adults’, ‘child marriages’, and ‘Africa’ were used to search the following databases: Google Scholar, JSTOR, Proquest, PubMed as well as websites of various international organisations active in mental, neurological and substance abuse disorders. After cautious deliberation and examining the title of the articles, research issues, and critical discussions in the abstract of the selected materials, only the most applicable literature on mental health and child marriages among young female adults in Africa was nominated. Table 1 shows the inclusion and exclusion criteria used to select relevant literature used in this paper.
3. Results
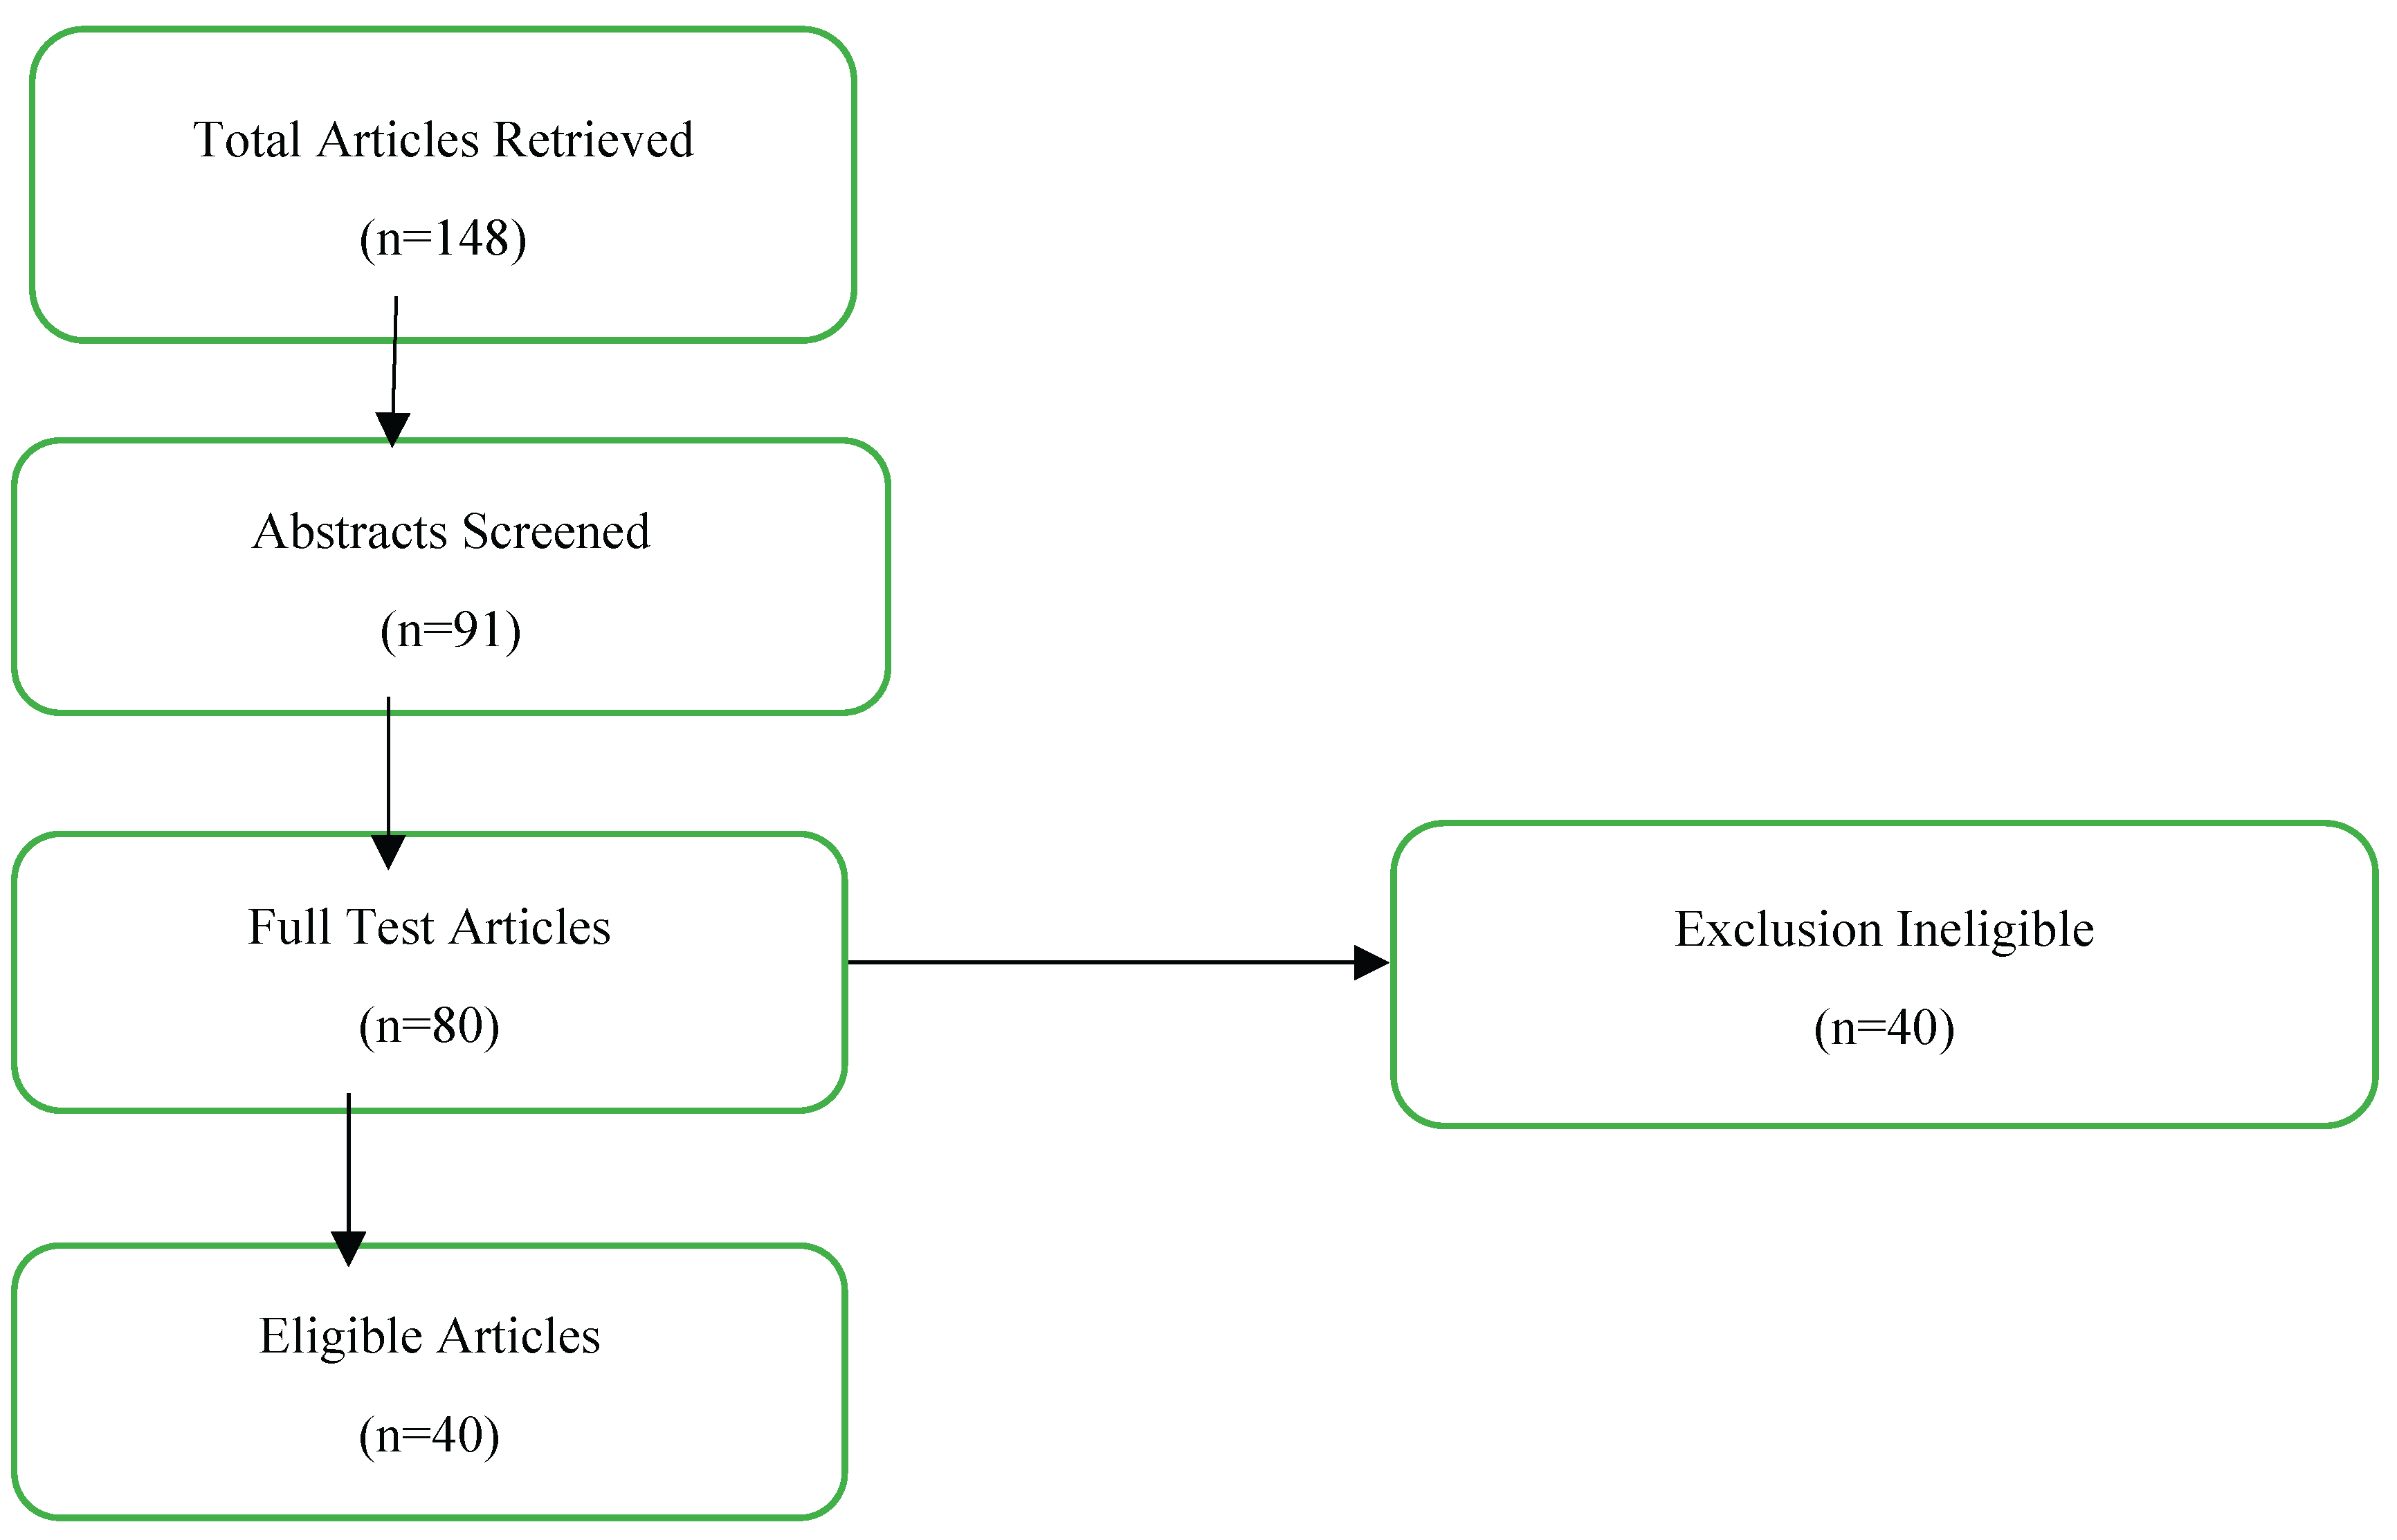
A total of one hundred and forty eighty (148) scholarly articles were retrieved. The oldest article was published in 2003 and the latest in 2023. Table 2 presents the number of articles, authors, sample information, research design, and focus area where data were extracted. Majority of the articles directly discussed child marriages and the mental health of young female adults in Africa. Grey literature on mental health and child marriages was also used to give a compelling background on the topic.
4. Characteristics of Included Studies
Characteristics of the 40 included studies are shown in Table 2.
Figure 1.
Flow diagram of articles searched.
Study Characteristics
The study employed 7 mixed methods, 5 qualitative, 12 quantitative, and 16 studies that did not specify their designs but were included because they met the inclusion criteria. The literature was from any African country and was published from 2003 to 2023. The limitation of the study was that most of the literature on mental health focused on the global north. Hence, the full methodology was apparently unavailable to avail in this study.
5. Discussion
We found the following themes regarding the implication of child marriage on young female adults' mental health. The discussion will begin with a brief background of child marriage, then implications of child marriage on young female adults’ mental health with themes, fertility and population growth, labor force and productivity, economic growth, healthcare, intimate partner violence, poverty, marital duties, and responsibilities.
5.1. A Brief Background of Child Marriages
Child marriage and early marriage has received public and academic dialogues, by worldwide international development organisations, generally showing that child and early marriage is a human rights defilement, with many negative health and social impact on girls and women (Chandra-Mouli, et al., 2013; Mathur et al., 2003; UNICEF, 2005). Research has also shown the association between a higher risk of early pregnancy increases the risk of maternal morbidity and maternal death (Svanemyr et al., 2012); significant risk of vesicovaginal and rectovaginal fistula (tearing of the wall separating the bladder or rectum from the vagina) (Meyer et al., 2007); raised risk of HIV infection (Bruce & Clark, 2004; Clark, 2004); and negative implications for mental health (Gage, 2013), poverty (Otoo-Oyortey & Pobi, 2003), reduces girls’ education prospects and reinforces gender inequality (UNICEF, 2006).
Msuya (2020) states that Africa is among the continents with a high rate of child marriages in the whole world. The age of consent in the majority of sub-Saharan African countries is 18 years, however, the marriage of children under the age of 18 remains high. As a result of that child marriage is among the goal targets of the United Nations’ Sustainable Development Goal (SDG) of gender equality (goal 5) (Wagenaar et al, 2020). Apart from its negative impact on physical growth, and emotional development, child marriage is also linked to mental health challenges young female adults go through as a result of getting married at a young age (John et al, 2019).
Research studies have shown that, in Africa, one in three girls is married by the age of 18 years and one in nine by the age of 15 years (UNFP, 2012). Although the largest number of child brides are in South Asian states, those with the highest rates of child marriage are in Africa. Thus, international, 39 percent of women aged between 20 and 26 years, were married before they attained the age of majority, are from sub-Saharan countries. Countries reported to have a high rate of child marriage in Africa are Niger (75 percent), Chad and Central Africa Republic (68 percent), Guinea (63 percent), Mozambique (56 percent), Mali (55 percent), Sudan and Burkina Faso (52 percent), Malawi (50 percent), Madagascar (48 percent), Eritrea (47 percent), Somalia (45 percent), Sierra Leone (44 percent), Zambia (42 percent) and Ethiopia (41 percent) (Maswikwa et al, 2015:19).
Globally, the practice of child marriage is a violation of childhood for both sexes, as 115 million men were married before the age of 18 years. Although boys who marry in childhood do not face the same risks and consequences as girls, due to biological and social differences, they have still experienced violation that shortens their childhood (Gaston et al, 2018). The highest level of child marriage is found in sub-Saharan Africa (UNICEF global databases (2018), based on DHS, MICS, and other national surveys (2010-2017)
5.2. Implications of Child Marriage on Young Female Adults’ Mental Health
5.2.1. Fertility and Population Growth
Child marriage and early childbearing have a critical influence on the development of opportunity, which is related to complex rates of fertility and population growth. At the same time reducing the level of prosperity per person, especially in African countries where there is high population growth (Efevbera et al, 2019). Young female adults who were married before 18 years have higher chances of having more children than young female adults who marry after 18 years or later. Child marriage reduces the ability of the family’s basic needs, for instance, food, education, and healthcare (Efevbera et al, 2019). Child marriage, however, becomes the most convenient solution for the majority of poor family households as they marry off their children to reduce the family’s basic needs burden.
It is estimated that young female adults who start having children below the age of 18 years have a 26 percent chance of having more children compared to those who are married above 18 years or older (Parsons et al, 2015). The increase in childbearing stresses the national budget of the country thus reducing the accessibility of basic services. Young female adults are forced to work for themselves to feed the children as national budgets to fund or provide accessible basic services become strained or none in the majority of African countries (Raj, 2010). Coming up with ways to end child marriages in Africa will reduce early births, thus increasing productivity and economic growth in Africa.
5.2.2. Labour Force and Productivity
Child marriage reduces participation in the labour force and puts young female adults at risk of morbidity that is caused by early and recurrent childbearing. Due to complications surrounding giving birth, young female adults will take time to recover from complications caused during birth (Burgess et al., 2022). Childbirth has physical, emotional, psychological, and social impacts as young female adults withdraw from labour force. Unable to work pose the family with a high risk of continuous poverty and affects human capital development (WHO 2014).
5.2.3. Economic Growth
Child marriages also affect economic growth, economic growth reduces poverty and enhances the quality of life (Burgess et al., 2022; UNFPA, 2012). However, the extent to which the poor partake in this development and share in its proceeds is considered by the degree to which development reduces poverty (UNFPA, 2012). The pace, pattern, and growth of child marriage, which affects child brides’ ability to take part in growth opportunities, has a crucial effect on attempts to reduce poverty (Msuya, 2020). Eradicating this phenomenon will certainly contribute to the reduction of mental health challenges young female adults go through (Burgess et al., 2022; UNFPA, 2012). Child marriage affects young female adults’ mental well-being in various ways, for instance, increased rates of malnutrition, isolation, developing suicidal thoughts, and depression (Burgess et al., 2022; UNFPA 2014 & Gage, 2013). Young female adults encounter maternal mortality and morbidity as a result of intimate partner violence (IPV) (Kidman, 2017; UNFPA 2014). The suffering that young female adults go through is a result of being financially dependent on their husbands/partners and in-laws. Being financially independent increases, the pressure child marriage has on their mental health. Unable to afford healthcare, put a strain on the household and ends up placing young female adults at risk of reducing productivity within the household and workforce (Burgess et al., 2022).
5.2.4. Healthcare
Failure to afford recommended healthcare for themselves also goes to their children who will suffer from poor nutrition, unable to get childhood immunisation, and infant mortality rate increases (Burgess et al., 2022). All these effects affect young female adults and end up suffering from mental health like depression, suicidal thoughts, anxiety, and self-harm (Khan et al., 2013). Those young female adults married as a result of forced marriage experience trauma, rape, and abuse (Burgess et al., 2022). They will be forced to start a family with strangers or older men who were married before or in marriage (Ahmed et al., 2013). In most instances, they do not consent to marriage. The whole process puts young female adults at risk of mental health breakdown and trauma in the long run.
Another implication of child marriage on the mental health of young female adults is unable to deliver children the normal way. They suffer long delivery and gestation, for instance, obstetric fistula, obstructed labour, and death (Meyer et al., 2007; Callaghan et al, 2015). Pregnancy difficulties and childbirth are the second foremost cause of death among young female adults between the age of 15 to 19 years, with nearly 70, 000 dying every year (WHO 2012). The health effects of early marriage go on to the children born by underage mothers. Infant mortality is 60 percent compared to those born with mothers above 18 years or older (UNICEF 2014).
5.2.5. Intimate Partner Violence
Young female adults are also unable to negotiate for safer sex with their partners/husbands which put them at risk of contracting sexually transmitted diseases and failing to do good child spacing (Ahmed et al., 2014). Higher expectations and pressure put upon early brides make them have children early when not ready. Young female adults cannot successfully do child spacing due to being unable to understand how to use family planning methods, the unavailability of healthcare institutions that provide family planning, fear, and cannot afford to buy family planning (UNFPA, 2014; John et al., 2019). All these negatively impact the mental health of young female adults.
5.2.6. Poverty
Children born to young female adults as a result of child marriages have high chances of suffering from poor nutrition, are underweight and prone to illness, and generally have a weak immune system (Ajayi et al., 2023). Growth and development for these children become slow and this affects even their attendance at school, and performance in the personal and public domain. Ajayi et al (2023) further postulate that the stress of having a child who is ill all the time and does not grow like any other child goes on to the mothers (young female adults). Visiting and staying in the hospital all the time is a traumatic experience, elevated with lack of financial support worsened the situation. All this escalates the mental health of young female adults into incapacitated situations.
Child marriage puts young female adults at a lifetime economic disadvantage (Msuya, 2020). Women who are educated, and employed can look after themselves, their families, children, and communities (Atilola, 2014). With poverty increasing in African communities, the hardest stricken population will be young female adults. Becoming an adult whilst being a child is a whole lot of stress (Burgess et al., 2022; Neetu et al., 2019), managing the situation as a child does not spare young female adults from developing lifetime mental health issues. They have no option but to deal with the predicament at hand.
Poverty causes depression and emotional distress in young female adults’ households. Families will be forced to marry off their daughters in exchange for payment of bride price and food. A study contacted in Niger and Ethiopia: ‘Child marriage and psychological well-being’ revealed that mental health disorders are more in children forced into marriage compared to those who marry in their own time. Brides married through forced marriage undergo stress and anxiety and lack purpose in life. They are not ready to take up any responsibilities that come with early marriage (John et al, 2019).
5.2.7. Marital Duties and Responsibilities
Child marriage results in the burden of marital and family responsibilities at a tender age like providing partner sexual satisfaction, childbearing, and child minding, responsible for household chores at the expense of enjoying childhood moments (John et al, 2019). Young female adults got into these responsibilities whilst young with no idea how to handle and solve issues that comes with marriage (Nasiroğlu & Semerci, 2017). Young female adults will not be emotionally, psychologically, and mentally ready (Khan et al., 2013). Support from the husband, in-laws, and their families will be barely minimum. Young female adults end up suffering from depression and emotional distress from tender ages and grow old with the illness.
5.2.8. Recommendations
Recommendations of this paper draw hugely from one of the reviewed studies conducted by Burgess et al., 2022 with the topic entitled ‘Overlooked and unaddressed: A narrative review of mental health consequences of child marriages’.

Table 3.
Caption.
| Future priorities for the mental health and child marriage field: final consensus statements | |
|---|---|
| Perspectives on early, child, and forced marriage and its relationship to mental health | 1. It is important to understand the mental health impacts of child marriage 2. Changing social norms is a mandatory part of reducing mental distress caused by the practice of child marriage 3. An individual’s location within society has a direct impact on the relationship between mental and child marriage (e.g. caste, ethnicity, race, sexuality, class, gender) 4. Intimate partner violence poses significant risks to the mental health of those married young 5. It is important to understand the intergenerational dynamics (i.e. in families or communities across generations) of child marriage. |
| Perspectives on policy approaches in the field | 1. Engagement with policy leaders in child marriage needs new forms of advocacy to highlight mental health as important. 2. Future policy (and research) must reflect the full range of communities where child marriage is practiced (e.g., Jewish Hasidic communities, Pentecostal/Mormon communities, Irish/Roma travelers, and Muslim communities) |
| Specific priority areas for understanding the mental consequences of child marriage on mental health | 1. The impact of child marriage on mental health can include withdrawal, depression, anxiety, suicidal tendencies, and a sense of abandonment. 2. The trauma experienced by people married young and impacts on their mental health 3. Understanding the mental health impacts of child marriage on the children of those married before 18 is important 4. Understanding the mental health impact among people experiencing child marriage, who feel that their marriage is not living up to their expectations is important. |
| Potential forms of mental health and psychological support | 1. Psychosocial treatments are beneficial for people married early, to address the mental health consequences of child marriage 2. Increasing the availability of general mental health support and services in rural or complex settings could benefit the mental well-being of individuals who married early 3. Social interventions to promote the mental health of people who married early should be community-based and locally grounded for the biggest impact 4. The social empowerment of women (e.g. through social-capital interventions) can help to increase autonomy and self-reliance, subsequently reducing child marriage and its impact on mental health |
6. Conclusions and Insight for Future Studies
The findings from the reviewed literature indicated that female young adults are vulnerable to developing mental health disorders. Through our systematic review study, child marriage and mental health in Africa are under-researched, which explained the noticeable dominance of grey literature in Table 2. Besides, previous studies focused more attention on how lived experiences of young female adults are potential threats to mental health disorders while significantly ignoring intervention solutions. The systematic review has therefore assisted to identify gaps in the literature and created opportunities for future studies.
We observed from the reviewed literature that mental health in young female adults is linked to early and child marriages (Callaghan et al, 2015), which is associated with young female adults low educational achievement, unemployment, substance abuse, risk behaviors, self-harm, poor provision of the healthcare system, and poverty (Kessler et. al, 2007). Their mental health is also associated with their family background, childhood abuse, violence in the neighborhood, loss, and grief, social exclusion, unintended pregnancy, and chronic diseases (WHO, 2021 & 2019; Dahmen et al, 2019 & Hodgkinson et al, 2014). Even their lifestyle includes being forced into sex work, trafficked, disabled, orphaned, HIV/AIDS, suicidal thoughts, and traumatic stress (Shiferaw et al., 2018).
Unfortunately, intervention programs were less investigated. Appropriate cultural-community-based policy initiations were also very silent in the reviewed studies. Future studies should be conducted in these critical identified areas to address child marriage in Africa.
Acknowledgments
We thank Pamela Makati from the Center of Graduate Support, University of the Free State, for English editing the work.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Ajayi, A.I., Chamdimba, E., Sawadogo, N., Gitahi, N., Tarnagda,A.M., Ilboudo, A.K., Munthali, A., Thakwalakwa, C., Otukpa, E.O., Ushie, B.A & Kabiru, C.W (2023). Socio-ecological factors associated with probable depression among pregnant and parenting adolescent girls: findings from a cross-sectional study in Burkina Faso and Malawi. Reproductive Health (2023) 20:38 . [CrossRef]
- Atilola, O (2014). Where lies the risk? An ecological approach to understanding child mental health risk and vulnerabilities in sub-Saharan Africa. Hindawi Publishing Corporation Psychiatry Journal Volume 2014, Article ID 698348, 11 pages. [CrossRef]
- Barnet B, Duggan AK, Devoe M & Burrell L. (2002). The effect of volunteer home visitation for adolescent mothers on parenting and mental health outcomes: a randomized trial. Arch Pediatr Adolesc Med. 156 (12):1216–22.
- Boyes ME., Cluver LD., Meinck F., Casale M, & Newnham E. (2019). Mental health in South African adolescents living with HIV: correlates of internalizing and externalising symptoms. AIDS Care. 31(1):95–104.
- Bruce, J & Shelley, C. (2004). "The implications of early marriage for HIV/AIDS policy," brief based on background paper prepared for the WHO/UNFPA/Population Council Technical Consultation on Married Adolescents. New York: Population Council.
- Burgess, RA, Jeffery M, Odero SA, Rose-Clarke K, & Devakumar, D (2022) Overlooked and unaddressed: A narrative review of mental health consequences of child marriages. PLOS Glob Public Health 2(1): e0000131. [CrossRef]
- Callaghan, J.E.M., Gambo,Y., Lisa, C & Fellin (2015).Hearing the silences: Adult Nigerian women’s accounts of ‘early marriages’ Feminism & Psychology, Vol. 25(4) 506–527.
- Chandra-Mouli, V., Camacho, A. V., & Michaud, P.A. (2013). WHO guidelines on preventing.
- early pregnancy and poor reproductive outcomes among adolescents in developing.
- countries. The Journal of Adolescent Health, 52(5), 517–522.
- Clark, S. (2004). Early marriage and HIV risks in sub-Saharan Africa. Studies in Family Planning, 35(3), 149–160.
- Cluver LD, Sherr L, Toska E, Zhou S, Mellins CA & Omigbodun O (2011). From surviving to thriving: integrating mental health care into HIV community and family services for adolescents living with HIV. Lancet Child Adolescent Health. [CrossRef]
- Daar AS, Jacobs M, Wall S, Groenewald J, Eaton J, Patel V, dos Santos P, Kagee A, Gevers A, Sunkel C, Andrews G, Daniels I, & Ndetei D. (2014). Declaration on mental health in Africa: moving to implementation. Glob Health ActionJun 13;7:24589. [CrossRef] [PubMed] [PubMed Central]
- Dahmen B, Konrad K, Jahnen L, Herpertz-Dahlmann B, & Firk C (2019). Mental health of teenage mothers: impact on the next generation. Nervenarzt 90 (3):243–50.
- Denyer, D. & Tranfield, D. (2009). “Producing a systematic review”, in Buchanan, D.A. and Bryman, A. (Eds), The SAGE Handbook of Organizational Research Methods, pp. 671-689.
- Entrepreneurship: Theory and Practice, Vol. 20 No. 1, pp. 55-72.
- Dewey, A. & Drahota, A. (2016) Introduction to systematic reviews: online learning module Cochrane Training https://training.cochrane.org/interactivelearning/module-1-introduction-conducting-systematic-reviews.
- Efevbera, Y., Bhabha, J., Farmer, P. et al. Girl child marriage, socioeconomic status, and undernutrition: evidence from 35 countries in Sub-Saharan Africa. BMC Med 17, 55 (2019). [CrossRef]
- Colleen Murray Gastón, Christina Misunas and Claudia Cappa (2019). Child marriage among boys: a global overview of available data, Vulnerable children and youth studies, Vol.14, No.3 219-228. [CrossRef]
- Gage, A. J. (2013). Association of child marriage with suicidal thoughts and attempts among.
- adolescent girls in Ethiopia. The Journal of Adolescent Health, 52(5), 654–656.
- Gore, FM, Bloem PJ, Patton GC, Ferguson J, Joseph V, & Coffey C (2011). Global burden of disease in young people aged 10–24 years: a systematic analysis. Lancet 377(9783):2093–102.
- Hodgkinson S, Beers L, Southammakosane C, & Lewin A. (2014). Addressing the mental health needs of pregnant and parenting adolescents. Pediatrics. 133(1):114–22.
- Kessler RC, Angermeyer M, Anthony JC, De Graaf R, Demyttenaere K, & Gasquet I (2007). Lifetime prevalence and age-of-onset distributions of mental disorders in the World Health Organization’s World Mental Health Survey Initiative. World Psychiatry 6 (3):168.
- Kidman R. (2017). Child marriage and intimate partner violence: A comparative study of 34 countries. Int J Epidemiol 46:662e75.
- Kitchenham, B. (2004), “Procedures for performing systematic reviews”, Keele, UK, Keele University, Vol. 33 No. 2004, pp. 1-26.
- Koblinsky M, Chowdhury ME, Moran A, Ronsmans C. (2012). Maternal morbidity and disability and their consequences: neglected agenda in maternal health. J Health Popul Nutr.30 (2):124-30. [CrossRef] [PubMed] [PubMed Central]
- Laurenzi CA, Gordon S, Abrahams N, du Toit S, Bradshaw M, & Brand A (2020). Psychosocial interventions targeting mental health in pregnant adolescents and adolescent parents: a systematic review. Reprod Health 17:1–15.
- Lund C, De Silva M, Plagerson S, Cooper S, Chisholm D, Das J, Knapp M, Patel V. (2011). Poverty and mental disorders: breaking the cycle in low-income and middle-income countries. Lancet.378 (9801):1502-14. Epub 2011 Oct 16. [CrossRef] [PubMed]
- Mathur, S., Greene, M., & Malhotra, A. (2003). Too young to wed: The lives, rights, and health of young married girls. Washington, DC: International Centre for Research on Women.
- Meyer, L., Ascher-Walsh, C. J., Norman, R., Idrissa, A., Herbert, H., Kimso, O., & Wilkinson, J. (2007). Commonalities among women who experienced vesicovaginal fistulae as a result of obstetric trauma in Niger. American Journal of Obstetrics and Gynecology, 197(1), 91–94.
- Maswikwa B, Richter L, Kaufman J, Nandi A. Minimum Marriage Age Laws and the Prevalence of Child Marriage and Adolescent Birth: Evidence from Sub-Saharan Africa. Int Perspect Sex Reprod Health. 2015 Jun; 41(2):58-68. [CrossRef] [PubMed]
- Msuya, N.H (2020). Child marriage: An obstacle to socio-economic development in sub-Saharan Africa. Journal for Juridical Science 45(2).
- Nasıroğlu, S., & Semerci, B. (2017). Mental assessment of girls consulting for early marriage and identifying risk factors. Anatolian Journal of Psychiatry, 18, 460-467.
- Neetu A. John, Edmeades, J & Murithi, L (2019). Child marriage and psychological wellbeing in Niger and Ethiopia BMC Public Health 19:1029. [CrossRef]
- Otoo-Oyortey, N., & Pobi, S. (2003). Early marriage and poverty: Exploring links and key.
- policy issues. Gender & Development, 11(2), 42–51.
- Parsons, J., Edmeades, J., Kes, A., Petroni, S., Sexton, M & Wodon, Q (2015) Economic Impacts of Child Marriage: A Review of the Literature, The Review of Faith & International Affairs, 13:3, 12-22. [CrossRef]
- Raj A. (2010). When the mother is a child: The impact of child marriage on the health and human rights of girls. Arch Dis Child 95:931e5.
- Roberts KJ, Smith C, Cluver L, Toska E, & Sherr L. (2021). Understanding mental health in the context of adolescent pregnancy and HIV in Sub-Saharan Africa: a systematic review identifying a critical evidence gap. AIDS Behav. [CrossRef]
- Khan, S & Noushad, S (2013). Early Marriage: A Root of Current Physiological and Psychosocial Health Burdens. International Journal of Endorsing Health Science Research (IJEHSR), Vol 2, Issue1.
- Shiferaw G, Bacha L, & Tsegaye D. (2018). Prevalence of depression and its associated factors among orphan children in orphanages in Ilu Abba Bor Zone, South West Ethiopia. Psychiatry J. 2018:7.
- Svanemyr, J., Chandra-Mouli, V., Christiansen, C. S., & Mbizvo, M. (2012). Preventing.
- child marriages: First international day of the girl child ‘‘my life, my right, end child.
- marriage’’. Reproductive Health, 9, 31.
- Tranfield, D., Denyer, D. & Smart, P. (2003), “Towards a methodology for developing evidenceinformed management knowledge by means of systematic review”, British Journal of Management, Vol. 14 No. 3, pp. 207-222.
- UNFPA (2014). Annual report: A year of renewal. New York, NY:UNFPA.
- UNFPA (2012). Annual report: Promise to keep. New York, NY: UNFPA.
- UNICEF (2018). Annual report. For every child, every right. New York, NY: UNICEF.
- U: New York, NY.
- UNICEF (2012). The state of the world’s children. Children in an urban world. New York, NY: UNICEF.
- UNICEF. (2006). Child protection information sheet: Child marriage. New York, NY:.
- UNICEF.
- UNICEF. (2005). Early marriage – A harmful traditional practice. New York, NY: UNICEF.
- Wagenaar BH, Hammett WH, Jackson C, Atkins DL, Belus JM, Kemp CG (2020). Implementation outcomes and strategies for depression interventions in lowand middle-income countries: a systematic review. Global Mental Health 7, e7, 1–30. [CrossRef]
- Webster, J. & Watson, R.T. (2002), “Analyzing the past to prepare for the future: writing a literature review”, MIS Quarterly, Vol. 26 No. 2, pp. 13-23.
- West N, Schwartz S, Mudavanhu M, Hanrahan C, France H, & Nel J (2019). Mental health in South African adolescents living with HIV. AIDS Care.31(1):117–24.
- Woollett N, Cluver L, Bandeira M, & Brahmbhatt H. (2017). Identifying risks for mental health problems in HIV positive adolescents accessing HIV treatment in Johannesburg. J Child Adolesc Ment Health 29(1):11–26.
- WHO. (2021). Adolescent mental health. Geneva: World Health Organisation https:// www. who. int/newsroom/ fact- sheets/ detail/adolescent mental health. Accessed 06 June 2023.
- WHO (2019). Child and adolescent mental health. Geneva: https://www. who. int/ mental_ health/ mater nal- child/ child_ adole scent/ en/. Accessed 06 June 2023.
- WHO (2014). Mental Health Atlas 2014. World Health Organisation Mental Health Atlas 2014 (WHO. int) Accessed 09 June 2023.
- WHO (2012). Risks to mental health: An overview of vulnerabilities and risks factors. World Health Organisation.
- WHO (2005). Department of Mental Health, Substance Abuse. Mental Health Evidence, & Research Team. Mental health atlas 2005. World Health Organization.
Table 1.
shows the inclusion and exclusion criteria used in selecting relevant articles.
| Inclusion criteria | Exclusion criteria | Outcomes of interest |
|---|---|---|
| Articles discussing mental health and child marriages | Child marriage studies without African countries as part of the sample/population | Mental health status of young female adults who were married before reaching 18 years |
| Articles discussing child marriages/mental health | Articles not published in English | Factors that caused mental health in young female adults as a result of child marriages |
| Articles presenting results of young female adults married before reaching the age of 18 years if they were part of the larger sample | Articles published before 2000 | Resulting in mental health impacts of child marriage. These include depression, psychological distress, anxiety, substance abuse, stress, and suicidal thoughts. |
| Grey literature on child marriage reports | ||
| Articles published in English | ||
| Articles with a sample drawn from any African country | ||
| Articles with key words mental health, young female adults, child marriages, and Africa | ||
| Articles with mixed, qualitative and quantitative studies, cross-sectional and observation, narrative review, baseline data | ||
| Articles published from 2000 to 2023 |
Table 2.
Data extraction table.
| S/N | Author | Sample Information | Research Design | Focus Area |
|---|---|---|---|---|
| 1 | Sadaf Ahmed Saima Khan, Malka Alia,& Shamoon Noushad (2013) |
Ethnicity/Country of Birth: Age range: 13 to 35 years Gender: Female Sample size:100 girls |
Method: Mixed methods Design: N/A Collection: Questionnaire Analysis: SPSS (Version 7) |
Psychological Impact Evaluation Of Early Marriages. |
| 2. | Olayinka Atilola (2014) | N/A |
Method: Mixed methods Design: Stratified random sampling Collection: face-to-face interview; semi-structured questionnaire Analysis: Stata software version 14 |
Where Lies the Risk? An Ecological Approach to Understanding Child Mental Health Risk and Vulnerabilities in Sub-Saharan Africa |
| 3 | Kidman R. (2017) |
Ethnicity/Country of Birth: Africa, Europe, Asia, and the Americas Age Range: 20–24 Gender: Female Sample size: 34 countries |
Method: Mixed methods Design: N/A Collection: demographic and health surveys Analysis: Logistic regression models. |
Child Marriage and intimate partner violence: a comparative study of 34 countries |
| 4 | Rochelle A Burgess, Farah Sheibani, Isabelle Kelly, Mairi Jeffery, Farirai Gumbonzvanda, Gemma Lewis, Asma Ashraf, Cristianne Connor, Solomon Mombeshora, and Nyaradzayi Gumbonzvanda (2023) |
Ethnicity/Country of Birth: Zimbabwe Age Range: N/A Gender: Male and females Sample size: 30 participants |
Method: Mixed methods Collection: Survey questions; Focus group discussion Analysis: Rapid thematic analysis |
Bringing an end to the silence: identifying priorities and solutions to addressing the mental health consequences of child marriage |
| 5 | Sadaf Ahmed, Saima Khan & Shamoon Noushad (2013) |
Ethnicity/Country of Birth: Age Range: 13-35 years Gender: Females Sample size: 100 girls |
Method: Mixed methods Design: N/A Collection: questionnaire Analysis: SPSS version 7 |
Early Marriage; A Root Of Current Physiological And Psychosocial Health Burdens |
| 6 | Burgess RA, Jeffery M, Odero SA, Rose-Clarke K, Devakumar D (2022) |
Ethnicity/Country of Birth: Countries in Global South. Age Range: N/A Gender: Females Sample size: 12 countries |
Method: Qualitative Design: narrative synthesis approach and cross-sectional |
Overlooked and unaddressed: A narrative review of mental health consequences of child marriages |
| 7 | Morvarid Irani & Robab Latifnejad Rousari (2023) |
Ethnicity/Country of Birth: Africa Age Range: NIL Gender: Females Sample size: Articles published 1946-2018 |
Method: Narrative review | Reproductive and Sexual Health Consequences of Child Marriage: A Review of Literature |
| 8 | Richard de Groot, Maxwell Yiryele Kuunyem, Tia Palermo (2018) |
Ethnicity/Country of Birth: Africa Age Range: 20-24; 20-29 Gender: Females Sample size: 594; 1349 |
Method: Quantitative Collection: Baseline survey Analysis: Ordinary least squares and Logistic regression models; Stata 14.2 (College Station TX) |
Child Marriage and associated outcomes in Northern Ghana: a cross-sectional study |
| 9 | Neetu A. John, Jeffrey Edmeades, and Lydia Murithi (2019) |
Ethnicity/Country of Birth: Niger and Ethiopia Age Range: 15 years or earlier Gender: Females |
Method: Mixed methods Collection: Baseline survey Analysis: Thematic qualitative and Statistical Analysis (Stata 14 software) |
Child Marriage and Psychological Wellbeing in Niger and Ethiopia. |
| 10 | Ajayi et al.(2023) |
Ethnicity/Country of Birth: Burkina Faso and Malawi Age Range: Adolescent girls Gender: Females Sample size:980; 669 |
Method: Quantitative study Design: Cross-sectional design Collection: a structured questionnaire Analysis: Statistical analysis (version 25) and Stata (version 15 for Windows) |
Socio-ecological factors associated with probable depression among pregnant and parenting adolescent girls: findings from a cross-sectional study in Burkina Faso and Malawi |
| 11 | Jane EM Callaghan, Yaganama Gambo, Lisa C Fellin (2015) |
Ethnicity/Country of Birth: Nigeria Age Range: 25-35 years Gender: Females Sample size: 6 women |
Method: qualitative approach exploratory study Collection: Individual interviews Analysis: interpretive phenomenological |
Hearing the silences: Adult Nigerian women’s accounts of ‘early marriages’ |
| 12 | Elizabeth Anokyewaa Sarfo, Joana Salifu Yendork & Anthony Vernon Naidoo (2022) |
Ethnicity/Country of Birth: Age Range: Gender: Females |
NA | Understanding Child Marriage in Ghana: The Constructions of Gender and Sexuality and Implications for Married Girls, Child Care in Practice |
| 13 | Suiqiong Fan and Alissa Koski (2022) |
Ethnicity/Country of Birth: sub-Saharan Africa and Asia Gender: Females Sample size: 58 articles |
Method: Systematic review Collection: Demographic and Health Surveys (DHS), or the World Fertility Surveys (WFS). Analysis: Synthesized results narratively. |
The health consequences of child marriage: a systematic review of the evidence |
| 14 | Suzanne Petroni, Mara Steinhaus, Natacha Stevanovic Fenn, Kirsten Stoebenau, Amy Gregowski (2017) |
Ethnicity/Country of Birth: sub-Saharan Africa Age Range: 14-18 years Gender: Male and Females Sample size: 4 countries: 805 girls; 79 participants |
Method: Mixed methods Design: Stratified design Collection: focus group discussions, in-depth interviews, key informant interviews, face-to-face surveys, Analysis: |
New Findings on Child Marriage in Sub-Saharan Africa |
| 15 | Sudhanshu Handa, Amber Peterman, Carolyn Huang, Carolyn Halpern, Audrey Pettifor, Harsha Thirumurthy (2015) |
Ethnicity/Country of Birth: Kenya Age Range: 12-49 years Sample size: 28 locations |
Method: Quantitative Design: Cluster randomized longitudinal Collection: baseline household survey and comprehensive demographic household survey Analysis: Empirical strategy |
Impact of the Kenya Cash Transfer for Orphans and Vulnerable Children on early pregnancy and Marriage of adolescent girls |
| 16 | Chandra-Mouli, V., Camacho, A. V., & Michaud, P.-A. (2013) |
Ethnicity/Country of Birth: Developing countries. Sample size: N/A |
Methodology: Report document | WHO guidelines on preventing early pregnancy and poor reproductive outcomes among adolescents in developing countries |
| 17 | Mathur, S., Greene, M., & Malhotra, A. (2003). |
Ethnicity/Country of Birth: Africa Sample size: N/A |
Methodology: N/A | Too Young to wed: The lives, rights, and health of young married girls. |
| 18 | UNICEF. (2005) |
Ethnicity/Country of Birth: Africa Age Range: Above 18 years Gender: Females Sample size: 50 countries |
Method: Quantitative Collection: Surveys Analysis: Multivariate analysis, Logistic analysis, Descriptive analysis, and logistic regression model |
Early marriage – A harmful traditional practice |
| 19 | Svanemyr, J., Chandra-Mouli, V., Christiansen, C. S., & Mbizvo, M. (2012) | Ethnicity/Country of Birth: Africa | Methodology: N/A | Preventing child marriages: First international day of the girl child |
| 20 | Meyer, L., Ascher-Walsh, C. J., Norman, R., Idrissa, A., Herbert, H., Kimso, O., & Wilkinson, J. (2007) |
Ethnicity/Country of Birth: Africa Age Range: 15.6 years and 17.3 years Sample size: 58 women |
Method: Quantitative Collection: questionnaire Analysis: SPSS statistical program (SPSS Inc, Chicago, IL) |
Commonalities among women who experienced vesicovaginal fistulae as a result of obstetric trauma in Niger |
| 21 | Bruce, Judith and Shelley Clark. (2004) |
Ethnicity/Country of Birth: Africa Sample size: 31 countries |
Methodology: Report document Collection: Demographic and Health Surveys Analysis: N/A |
The implications of early marriage for HIV/AIDS policy," brief based on a background paper prepared for the WHO/UNFPA/Population Council Technical Consultation on Married Adolescents. |
| 22 | Gage, A. J. (2013) |
Ethnicity/Country of Birth: Ethiopia Gender: Female Sample size: 31 countries |
Method: Quantitative Collection: Cross-sectional survey Analysis: Multilevel logistic regression |
Association of child marriage with suicidal thoughts and attempts among adolescent girls in Ethiopia. |
| 23 | UNICEF (2006) |
Ethnicity/Country of Birth: Gender: Female |
Methodology: Document Report Collection: Demographic Health Surveys and Multiple Indicator Cluster Surveys |
Child protection information sheet: Child marriage |
| 24 | Clark, 2004 | NA | Methodology: N/A | Early Marriage and HIV Risks in sub-Saharan Africa |
| 25 | Otoo-Oyortey & Pobi, 2003 | NA | Methodology: N/A | Early marriage and poverty: Exploring links and key policy issues. |
| 26 | Msuya (2020) | NA | Methodology: N/A | Child marriage: An obstacle to socio-economic development in sub-Saharan Africa. |
| 27 | Wagenaar et al, 2020 |
Sample size: 8714 studies |
Method: Quantitative Analysis: Stata 15 |
Implementation outcomes and strategies for depression interventions in low- and middle-income countries: a systematic review |
| 28 | UNFP, 2012 |
Gender: Female Sample size: 23 sub-Saharan countries |
Methodology: Document report | Annual report: Promise to keep |
| 29 | Maswikwa et al, 2015 |
Ethnicity/Country of Birth: Africa Age Range: 18 years Gender: Female Sample size: 12 sub-Saharan African countries |
Method: Quantitative Collection: Demographic and Health Surveys (DHS), Child Marriage Database, Global Resource and Information Directory (GRID) Analysis: Descriptive analyses |
Minimum Marriage Age Laws and the Prevalence of Child Marriage and Adolescent Birth: Evidence from Sub-Saharan Africa |
| 30 | Gaston et al, 2018 |
Age Range: 15-49 Gender: Female |
Methodology: N/A | Child marriage among boys: a global overview of available data |
| 31 | UNICEF 2018 | NA | Methodology: Document Report | Annual report. For every child, every right. |
| 32 | Efevbera et al, 2019 |
Age Range: 15 to 49 Gender: Female Sample size: 35 African countries (249,269 women) |
Method: Quantitative Collection: 103 Demographic and Health Surveys (DHS) Analysis: Statistical analysis |
Girl child marriage, socioeconomic status, and undernutrition: evidence from 35 countries in Sub-Saharan Africa |
| 33 | Parsons et al, 2015 | NA | Method: Literature review | Economic Impacts of Child Marriage: A Review of the Literature |
| 34 | Raj, 2010 | NA | Methodology: N/A | When the mother is a child: The impact of child marriage on the health and human rights of girls. |
| 35 | WHO 2014 | NA | Methodology: World report | Mental health Atlas |
| 36 | UNFPA 2014 | NA | Methodology: Document report | Annual report: A year of renewal |
| 37 | UNICEF 2014 | NA | Methodology: Document report | Annual Report 2014 Our Story |
| 38 | WHO (2012) | NA | Methodology: World report | Risks to mental health: An overview of vulnerabilities and risks factors |
| 39 | Neetu et al., 2019 |
Ethnicity/Country of Birth: Ethiopia and Niger Age Range: 18–45 Gender: Female Sample size: 2764 and 4149 |
Method: Quantitative Collection: questionnaire |
Child Marriage and psychological wellbeing in Niger and Ethiopia |
| 40 | Nasiroğlu & Semerci, 2017 |
Ethnicity/Country of Birth: Age Range: 16 and 17 Gender: Female Sample size: Eighty-one cases- 80 girls |
Method: Quantitative Analysis: SPSS for Windows 22.0 |
Mental assessment of girls consulting for early marriage and identifying risk factors |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.