

Submitted:
13 November 2026
Posted:
16 November 2026
You are already at the latest version
Abstract
Background/Objectives: Air pollution (AP) has been linked to an increased risk of ischemic heart disease (IHD). Numerous studies have analysed the impact of AP on myocardial infarction (MI), yielding conflicting results that could be attributed to the selection of cases and regional differences in pollution and cardiovascular risk. Methods: The relationship between the incidence of ST-segment-MI with demonstrated culprit plaque (CP-STEMI) and the exposure to several air pollutants in previous days was studied in municipalities of the metropolitan area of Madrid (Spain, 2013-2018) using linear quasi-Poisson regressions. The municipality’s daily pollution exposure was estimated as the average of all AP measurement stations weighted by the inverse of the distance to the centroid of the municipality. Results: 4,406 CP-STEMI cases were registered. NO2 surpassed the World Health Organisation recommended level more than 50% of the days. Particulate matter <2.5 microns (PM2.5) surpassed recommended level 16% of the days and SO2 and CO none. For the two-day lag exposure model, there was a significant increase in CP-STEMI in days with an increase to the 2nd tertile vs the 1st tertile of PM2.5 (aRR 1.10, 95%CI:1.00-1.20, p=0.043). The difference between the 1st and 3rd tertiles remained positive but not significant. A clear association of CP-STEMI and cold was found, but not for the rest of pollutants. Conclusions: This study suggests an increased risk of CP-STEMI independently associated with PM2.5 and confirms the effect of cold, in a region with low risk of IHD, temperate climate and reasonably controlled levels of environmental pollution.
Keywords:
ST elevation myocardial infarction
; ischemic heart disease
; cardiovascular risk factors
; air pollution
; particulate matter
; cold temperature
1. Introduction
Cardiovascular diseases are the leading cause of death in developed countries. They impose a significant financial burden on healthcare systems and reduce quality of life. Ischemic heart disease (IHD) and its various manifestations, including acute coronary syndrome, are responsible for the highest number of deaths [1]. An individual’s cardiovascular risk is usually assessed using scoring systems that consider their cardiovascular risk factors. However, this individual-level approach does not explain why a patient with a given risk experiences an acute event at a specific time rather than another. A group-level ecological risk analysis could explain temporal variations of incidence of acute IHD events in the population. These variations appear to depend on environmental risk factors such as temperature, epidemics (particularly influenza) and ambient pollution [2].
Air pollution has been linked to a wide range of diseases, particularly respiratory and cardiovascular conditions [3]. Airborne particulate matter and gases such as carbon monoxide, sulphur dioxide, nitrogen monoxide, nitrogen dioxide and ozone, are naturally present in the air. The concentration of these substances can increase significantly due to human activity and natural phenomena such as desert dust clouds. The link between particulate matter and gaseous pollutants and cardiovascular disease can be explained by mechanisms such as endothelial damage, an increased inflammatory response, oxidative stress, mitochondrial damage and potential genotoxic effects. These can lead to atherosclerosis, hypertension, hypercoagulable states and an imbalance between the supply of and demand for energy in cardiac tissue [4,5]. Numerous studies have analysed the potential impact of these pollutants on myocardial infarction, yielding conflicting results.
There are many reasons that may explain the variability in the results of published studies. One of these is the difference in pollution levels to which the populations included in these studies are exposed. For example, the meta-analysis by de Bont et al (2022) shows that levels of particulate matter smaller than 2.5 micrometres (PM2.5) are 8.5 times higher in Bangladesh than in developed Western countries, with most of the studies concentrated in China, where concentrations were four times higher [3]. The origin of the pollutants, whether natural or not, could alter their effect and explain situations such as those described in the study conducted by Pope et al. (2015) in Utah, USA [6]. This is an area characterised by significant variations in airborne particulate matter due to natural causes, in which no association was found between the risk of MI and PM2.5 concentrations below 25 μg/m³, which are usually associated with an increased risk in other studies [3].
There are also complex interactions between the various pollutants. PM2.5, for example, can be particularly harmful due to its ability to absorb oxidising compounds on its surface [5]. Since data from air quality monitoring stations are usually quantitative only, these interactions could go unnoticed. Variability could also be due to the different groups of diseases analised in the studies. For example, it has been published that ST-segment elevation MI (STEMI) could be preferentially associated with PM2.5 pollution [6], while other authors describe just the opposite through a particular interaction with non-ST segment elevation MI [7]. Results may vary depending on the selected disease, which makes studying specific pathological processes worthwhile.
This study aimed to analyse, from an ecological perspective, the relationship between various air pollutants and the incidence of primary myocardial infarction with plaque rupture confirmed by coronary angiography in the Autonomous Community of Madrid (ACM), Spain, an European region with low cardiovascular risk.
2. Materials and Methods
2.1. Reference Population and Study Sample
This study’s reference population consists of individuals aged 18 and over who resided in the Autonomous Community of Madrid (ACM) between 1st January 2014 and 31st May 2018. During the study period, the population ranged from 5,350,306 to 5,543,970 inhabitants [8]. The study sample consists of STEMI cases included in the Código Infarto Madrid registry during this period for which the plaque responsible for the myocardial infarction (MI) was identified via cardiac catheterization. Código Infarto Madrid is a healthcare network designed to coordinate the management of STEMI in the ACM described in depth elsewhere [9]. After presenting a research proposal to the Código Infarto Madrid committee, the researchers obtained an anonymised version of the registry. They used this to obtain the municipality in which the patient resides, their age and sex, the date and time of symptom onset, and the dates and times of various care steps, including cardiac catheterization and its results. Only those cases of STEMI in which an emergency cardiac catheterisation confirmed the presence of a culprit plaque were included (CP-STEMI). To record daily events, the date and time first recorded during the alert were taken as the date of the event.
2.2. Meteorological Data
The meteorological data were obtained from the Spanish Meteorological Agency (AEMET), which operates a national network of weather stations. The climate of the ACM is classified as temperate continental, characterized by significant annual temperature variations. Since it is a relatively small territory (8,030 km²), temperature variations among its municipalities are minor. Therefore, measurements from a single observatory located in the town of Getafe have been used as a reference for the entire ACM [10,11].
2.3. Air Pollution Data
The air pollution data were obtained from the Air Quality Networks of the ACM and the Madrid City Council. These two networks are integrated into the National Air Quality Information System, which has unified records and databases. The ACM Air Quality Network, consists of twenty-four fixed monitoring stations and is under the Regional Ministry of the Environment and Spatial Planning [12]. Data from this network were obtained upon request following submission of a project proposal. The Madrid City Council’s Air Quality Monitoring System consists of twenty-four fixed stations and one mobile unit [13]. The stations are classified as urban background, urban traffic, suburban, heavy metal sampling points, and manual PM2.5 sampling points. For this study, only urban background stations were considered. Suburban stations were excluded because they correspond to uninhabited green areas. Manual sampling points were also excluded. The data were obtained via direct download from the Madrid City Council website [14].
Daily data from both networks includes carbon monoxide (CO), sulfur dioxide (SO₂), particulate matter with a diameter of 10 micrometers or less (PM10) and particulate matter with a diameter of 2.5 micrometers or less (PM2.5), nitrogen dioxide (NO₂), and ozone (O₃) from all monitoring stations. The recommendations of the World Health Organisation (WHO) are taken as a guideline for acceptable levels of environmental pollution [15].
2.4. Ethical Considerations
All personal patient data from the database of Código Infarto Madrid were deleted by the authority responsible for maintaining that database before making them available to researchers. All the data used in this study is anonymised and therefore it is not possible to identify patients based on the data included in the datasets. The study did not involve any modification of accepted clinical management protocols or animal experimentation. The Research Ethics Committee of one of the hospitals included in Código Infarto Madrid previously approved the study (MR 02/2023 as an extension of OE 10/2017, University Hospital Príncipe de Asturias Ethics Committee). The committee explicitly included an exemption from requesting informed consent from the patients included in the study. The committee has since approved expanding the study to include variables related to air quality.
2.5. Statistical Analysis
2.5.1. Summary Statistics and Crude Associations
The unit of analysis is not the individual but the municipality. Each MI case was assigned to the municipality where the patient was registered in the health service according to their unique identifier number (CIPA). If the case did not have a CIPA (e.g. people not living in Madrid) then the MI was assigned to Madrid municipality as this is where most of the non-residents tend to suffer MIs. The daily exposure to pollution in each municipality was estimated as a weighted mean of the daily mean levels across all the stations in the ACM, weighting by the inverse of the distance from the station to the centroid of the municipality [16]. Therefore, measures from stations close to the municipality contributed more to the weighted mean than measures from stations further away. The estimation was done for each pollutant on a daily basis, and a time series dataset was developed with a row per day per municipality, with the number of MIs, the estimated levels of each pollutant and the daily minimum temperature and minimum pressure in the ACM.
2.5.2. Descriptive Analysis
The levels of each pollutant, minimum temperature and minimum pressure were summarised across the study period using descriptive statistics (mean, standard deviation). The proportion of days in which the levels of each of the pollutants surpassed the WHO recommended levels was calculated, except for ozone as the WHO limits are based on 8-hour averages and the ACM data is for 24-hour periods [15]. The limits are: 40µg/m3 for SO2, 4mg/m3 for CO, 25µg/m3 for NO2, 15µg/m3 for PM2.5 and 45µg/m3 for PM10. The daily number of MIs was summarised using mean and standard deviation (SD). These results were presented separately for Madrid capital and all other municipalities, and by season as well as overall. Seasons were defined as: Winter (December-February), Spring (March-May), Summer (June-August) and Autumn (September-November). Pairwise Pearson correlation coefficients were calculated between all pollutants and minimum temperature and minimum pressure measures.
2.5.3. Multivariable Models
Exposure days were classified into tertiles for each pollutant within each municipality. The association between the tertile of each pollutant and the number of daily MI was estimated using a conditional quasi-Poisson model to account for overdispersion in the number of MIs. The models were conditioned on strata defined by municipality, adapting the case-crossover approach presented by Tobias et al. [17] to account for unmeasured differences between municipalities e.g. population size. The models were also adjusted for day-of-week, month, year, minimum temperature and minimum pressure. Previous studies have shown that pollution levels change according to weekends vs weekdays and that cardiovascular events are more frequent on certain days [18]. Month and year adjustment account for seasonality and trend.
For each pollutant, four models were fitted, respectively, with the exposure defined by the number of previous days considered when defining the exposure (lags): lag0: no previous days are used, only pollutant levels of same-day are considered; lag1: average between same-day and previous day’s exposure; lag2: average between same-day’s and two previous days’ exposure and lag3: average between same-day’s and three previous days’ exposure. The lagged exposure was then classified into the municipality’s tertiles. The adjustment variables minimum temperature and minimum pressure were included with the same lag-structures as the main exposure in each model.
Models with no pollutants were fitted to estimate the association between number of daily MIs and minimum temperature and minimum pressure using quasi-Poisson regressions, adjusted for day-of-the-week, month and year. The models were conditioned on strata defined by municipality and repeated the same four lag structures of temperature and pressure as in the pollutant models.
The adjusted rate ratio (aRR) and 95% confidence interval (CI) for a change from the 1st to the 2nd tertile or from the 1st to the 3rd tertile of the exposure under analysis was extracted from each pollution model. For the meteorological model, the aRRs were presented for a 5°C increase in minimum daily temperature and a 10 hPa increase in minimum daily pressure. We did not adjust for multiple testing.
R v4.5.1 software (R Core Team, 2026) was used for all statistical analyses. Code for the conditional quasi-Poisson models were adapted from a tutorial presented by Tobias et al. [17].
3. Results
In total, there were 6,042 admissions with CP-STEMI in ACM, with at least one admission in each of 144 municipalities of ACM between 1st January 2014 and 31st May 2018.
Due to model fitting issues when including rural municipalities with few events, we present results for only the Metropolitan Area of Madrid (MAM) consisting of Madrid capital and 36 surrounding municipalities [19]. MAM received 72.9% (4,406) of all admissions in ACM, and of those 2,684 (60.9%) were in Madrid capital and 1,722 (39.1%) in the surrounding municipalities. The mean daily number of MI admissions was 1.67 (SD=1.42) for people registered in Madrid capital, compared to 1.07 (SD=1.14) for people registered in all other 36 municipalities.
All air pollution measures, except PM10 and ozone, tended to be higher in Madrid capital than in the surrounding municipalities and higher in winter and autumn compared to spring and summer (Table 1).
CP-STEMI: Myocardial infarction with ST segment elevation and demonstrated culprit plaque.
Of all the air pollution measures, NO2 passed the WHO recommended level the highest proportion of days during the study period: 88.3% days in Madrid capital and 59.0% in the other municipalities. There were no days where the levels of SO2 nor CO surpassed the WHO recommended levels. There was a very small proportion of days where PM10 was higher than the WHO recommended level (2.9% in Madrid capital and 3.4% in other municipalities). However, PM2.5 surpassed the WHO recommended level a higher proportion of days: 16.3% in Madrid capital and 16.0% in other municipalities.
The mean minimum daily temperature was 10.69°C (SD=7.04), ranging from 3.07°C (SD=3.22) in winter to 19.37°C (SD=3.19) in summer. The mean minimum daily pressure was 944.21 hPa (SD=6.38), ranging from 943.11 hPa (SD=5.53) in spring to 946.80 hPa (SD=8.82) in summer.
Minimum daily temperature was weakly positively correlated with minimum daily pressure (r=0.13), with PM2.5 (r=0.02) and with PM10 (r=0.23), but strongly correlated with O3 (r=0.63). On the other hand, minimum daily temperature was negatively correlated with SO2 (r=-0.39), CO (r=-0.55) and NO2 (r=-0.38). Air pollution measures are pairwise positively correlated with each other except O3, that has a weak to strong negative correlation with all other air pollution measures (Figure 1).
Most associations between the level of air pollution exposures and daily CP-STEMI admissions were non-significant (Table 2). For the model with lag of two days, there was a significant increase in CP-STEMI admissions in days with an increase to the 2nd tertile compared to the 1st tertile of PM2.5 (aRR 1.10, 95% CI: 1.00 to 1.20, p=0.043). The difference between the 1st and 3rd tertiles of PM2.5 was not significant, but the direction of the association remained positive. For the three models with lags, the direction of the association between level of PM2.5 and number admissions was also positive. In the model with a 3-day lag, an increase in carbon monoxide from 1st to 2nd tertile was associated with fewer admissions (aRR: 0.90, 95% CI: 0.81 to 0.98, p=0.023). However, the direction of the association between carbon monoxide and MI admissions was not consistent across the models: in the lag 1 model, increasing carbon monoxide was associated with higher CP-STEMI admissions (although not significant).
Minimum daily temperature was associated with CP-STEMI admission in all four models, irrelevant of lag structure used. For example, a 5°C reduction in the average of the minimum temperatures taken over the same-day and the previous three days (Model 4: lag 3) was estimated to increase risk of CP-STEMI admission by 14.4%, controlling for the day-of-week, month and year and minimum daily pressure (95% CI: 8.2% to 20.2%, p<0.0001). Minimum daily pressure was not significantly associated with CP-STEMI admission none of the four models, irrelevant of lag structure used (Table 2).
4. Discussion
Our study shows a strong association between cold temperatures and the daily incidence of MI. It also suggests a less pronounced but consistent association with atmospheric levels of PM2.5, whilst no consistent associations were observed with other air pollutants included in the analysis: sulphur dioxide, carbon monoxide, nitrogen dioxide, ozone and PM10. These results were obtained from a geographically concentrated population, with numerous air quality monitoring stations, relatively low levels of pollution, and by analysing the incidence of a well-characterised pathophysiological phenomenon—primary myocardial infarction—since in all cases the rupture of a coronary atheromatous plaque was confirmed by cardiac catheterisation. Compared with the vast majority of published studies, this case selection was certainly limited in terms of the number of subjects included, but it allowed for the exclusion of all diagnoses of secondary myocardial infarction, which can cause confusion in the results due to their different pathophysiology.
The link between cold weather and acute ischaemic events has been widely documented [20], although this is not consistent across the literature, even in some cold regions [21,22]. It is not difficult to explain this variability by the differences in climate across the geographical areas analysed. In our case, with a temperate continental climate, characterised by few episodes of temperatures below 0°C and very frequent heatwaves [9], we can observe this association with lower temperatures rather than with extremely high ones, thereby supporting the link between cold and primary myocardial infarction even in temperate climates. Other studies have described an interaction between cold and other demographic and environmental factors, such as age, male gender, PM2.5 levels and living in more temperate areas [23].
Air pollution, whether caused by human activity or associated with natural phenomena, is linked to human health [3]. For the specific case of IHD, various mechanisms that may cause the condition have been described [4]. Numerous studies have also been published aiming to demonstrate these relationships, with varying results depending on the specific presentation of IHD analysed, the different pollutants and the different regions. For example, in the case of ozone, a recent meta-analysis states that there may be a link between its atmospheric concentration and the risk of myocardial infarction, although with considerable heterogeneity that could depend on the regions analysed and their economic status [24]. This fact may help to explain why a potentially harmful greenhouse gas causes disease in certain environments, but why this has not been demonstrated in the specific case of primary myocardial infarction in our region. Furthermore, the close correlation between ozone levels and temperature in our environment could explain the absence of any noticeable effect, owing to the protective effect of temperature on the risk of CP-STEMI.
There are also conflicting findings in published studies on particulate matter smaller than 5 and 10 micrometres. In addition to the regional variations already mentioned, these differences may be explained by methodological factors. Among other things, they may depend on the time intervals used to record pollutant levels, as some pollutants may have an immediate effect whilst others may have a delayed effect (lag). A meta-analysis comprising 26 studies from around the world showed a clear association between the first few hours of exposure to PM2.5 and the risk of MI; this association was somewhat less significant for PM10 and absent for ozone, nitrogen dioxide, sulphur dioxide and carbon monoxide [25]. These results, which are similar in direction to the findings of our study, are less directly comparable due to the fact that our data are solely on a daily basis. Another meta-analysis on the relationship between PM10 and the risk of MI has reported variable results depending on both the type of infarction selected and the latency period following exposure [26], generally showing a positive association which we have not found for these larger particles. Long-term exposure to particulate matter also appears to cause long-term damage [27], a fact that the design of our study does not allow us to analyse.
The differences in pollution levels observed across the various published studies can be wide-ranging. In countries such as Australia, Canada, the United States, Sweden and Finland, the average annual PM2.5 concentration in 2019 was below 10 μg/m³. The highest global values that year were recorded in Bangladesh, at an average of 83.3 μg/m³ per year. Much of the research on the effects of these particles has been conducted in China, where average concentrations can reach 39.1 μg/m³ [3]. A nationwide study conducted among hospitals of the Spanish National Health System has shown that maximum 3-day average PM2.5 levels exceeding 10μg/m3 were associated with an increased risk of hospital discharges of any type of MI [28]. During the period of our study, mean air concentrations of PM 2,5 were around 10 µg/m3 and only 16% of the time exceeded the recommended values by the OMS. In our sample, all pollutant concentrations were usually lower than recommended except for nitrogen dioxide. This could mean that levels of pollutants recommended by the WHO are quite adequate to prevent an increase of risk for primary myocardial infarction.
The nature of particulate matter can also be associated with their deleterious effects. Studies such as that conducted by Pope et al. (2015) in Utah, USA, in an area with high variability in PM2.5 concentrations throughout the year due to natural meteorological causes, found no significant association between MI incidence and PM2.5 concentrations lower than 25 μg/m³, but described it for higher concentrations [6]. PM2.5 can be particularly harmful due to its ability to absorb oxidising compounds on its surface, especially when derived from combustion [29]. These compounds are not found in PM2.5 from sources such as sea salt or airborne dust [30]. Data from air quality monitoring stations are usually quantitative only. A cross-sectional study conducted in 16 Canadian cities found that the risk of MI was higher in cities with similar concentrations of these particles but different associated compounds when the particles were associated with substances having greater oxidising capacity and higher concentrations of O₃ and NO₂ [31]. In our study we could not find an increase of risk associated with oxidizing gases, such as Ozone and Nitrogen dioxide. Curiously, PM2.5 air concentration was directly correlated with temperature, suggesting a role of Saharan dust and forest fire smoke over PM2.5 concentrations, very frequent during the summer in Spain [32]. This type of particulate matter could be less harmful than those due to anthropogenic pollution [31].
Most studies have not distinguished between different types of heart attack. When a distinction is made between STEMI and NSTEMI, some studies suggest that ambient PM2.5 concentrations are primarily associated with the risk of the first [6], whilst others see a connection with both types [33], and others suggest the opposite [7]. There are primarily clinical management considerations involved in distinguishing between STEMI and NSTEMI, while secondary MI—not caused by plaque rupture—are more likely to be found in the NSTEMI group [2]. Our study included only STEMIs in which plaque rupture was demonstrated, which supports a pathophysiological link between primary myocardial infarction (due to atherosclerotic plaque rupture) and PM2.5 exposure.
4.1. Limitations
This study has the limitations inherent to an ecological study, in which the exposure of each individual has not been assessed, nor has it been compared with that of other healthy individuals.
Hourly pollution readings were not used, which limits the ability to determine very short-term effects. Long term exposure has not been assessed, also. We used data on the place where each subject resided, rather than the hospital where they were treated, as we considered exposure at the place of residence more likely than in the vicinity of the healthcare centre. It might have been preferable to use data on the location where the event occurred, but this was not available to us. The very mobility of the population in our region—where many people commute from the metropolitan area to the capital, and vice versa—makes it practically impossible to determine the actual hourly level of pollution to which each patient is exposed. For this reason, we opted to use daily values and calculate pollution gradients between the various measurement points, thereby enabling an estimate of pollution levels at the subjects’ places of residence.
The sample size is limited both by the study’s confinement to a single region and by the selection of cases in which a ruptured atheromatous plaque was confirmed. It is possible that a larger sample might reveal effects that have remained hidden, but the current sample size would not invalidate the findings described.
4.2. Strengths
The study analysed a single pathological mechanism underlying myocardial infarction, which makes it possible to rule out false positives in the diagnosis, as well as to exclude secondary and iatrogenic infarcts from the analysis, thereby increasing the specificity of the findings. Furthermore, the study focused on a geographically concentrated population. National or international studies, whilst having the advantage of analysing a large number of cases, have the drawback of greater variability in potential confounding variables. For example, levels of human development or income, climatic variations between regions, the mean age of the population, healthcare provision or PM2.5 levels caused by sea salt. All these sources of potential variation can be minimised by analysing a smaller geographical area, which could lend greater consistency to the findings.
5. Conclusions
Our study shows an increased risk of primary myocardial infarction, due to coronary atheromatous plaque rupture, clearly associated with low temperatures and possibly associated to particulate matter smaller than 2.5 micrometres. No association was found between other pollutants analysed and the risk of myocardial infarction. These findings have been observed in an environment where extremely low temperatures are rare, and where pollution levels do not usually exceed WHO recommendations. Our results do not rule out the possibility that higher levels of pollution could be associated with higher risk, but suggest that Public Health recommendations to control pollution could be effective.
Author Contributions
“Conceptualization, E.GS. and A.GL.; methodology, I.L.; D.P:; A.GL.; formal analysis, I.L; D.PM.; investigation, E.GS.; I.L.; data curation, I.L.; E.GS.;; writing—original draft preparation, E.GS.; I.L.; A.GL.; writing—review and editing, E.GS.; I.L.; D.PM.; A.GL.; supervision, D.PM.; A.GL.; project administration, A.GL. All authors have read and agreed to the published version of the manuscript.”.
Funding
The publication of this paper has been possible thanks to the financial support of the Interhospital Foundation for Cardiovascular Research (FIC, Madrid, Spain).
Institutional Review Board Statement
The Research Ethics Committee of one of the hospitals included in Código Infarto Madrid previously approved the study (MR 02/2023 as an extension of OE 10/2017, University Hospital Príncipe de Asturias Ethics Committee). The committee has since approved expanding the study to include variables related to air quality.
Informed Consent Statement
The committee explicitly included an exemption from requesting informed consent from the patients included in the study.
Data Availability Statement
The data presented in this study are available upon request to the corresponding author, as prior consultation with the Codigo Infarto Madrid Committee—the competent authority that owns the data—is required.
Acknowledgments
During the preparation of this manuscript, the authors used GhatGPT 5.2 to improve the quality of the figures included. The authors have reviewed and edited the output and take full responsibility for the content of this publication.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ACM | Autonomous Community of Madrid |
| AEMET | Spanish Public Agency of Meteorology |
| AP | Air Pollution |
| aRR | Adjusted Rate Ratio |
| CI | Confidence Interval |
| CIPA | Patient unique identifier number |
| CP-STEMI | STEMI with demonstrated culprit plaque |
| IHD | Ischemic Heart Disease |
| MI | Myocardial Infarction |
| NSTEMI | Myocardial Infarction without ST Segment Elevation |
| STEMI | Myocardial Infarction with ST Segment Elevation |
| SD | Standard Deviation |
| WHO | World Health Organisation |
References
- GBD 2023 Causes of Death Collaborators. Global burden of 292 causes of death in 204 countries and territories and 660 subnational locations, 1990-2023: a systematic analysis for the Global Burden of Disease Study 2023. Lancet 2025, 406(10513), 1811–1872. [CrossRef] [PubMed]
- García-Lledó, A.; Rodríguez-Martín, S.; Tobías, A.; García-de-Santiago, E.; Ordobás-Gavín, M.; Ansede-Cascudo, J.C.; Alonso-Martín, J.; de Abajo, F.J. Relationship Between Influenza, Temperature, and Type 1 Myocardial Infarction: An Ecological Time-Series Study. J. Am. Heart Assoc. 2021, 10(8), e019608. [Google Scholar] [CrossRef] [PubMed]
- de Bont, J.; Jaganathan, S.; Dahlquist, M.; Persson, Å.; Stafoggia, M.; Ljungman, P. Ambient air pollution and cardiovascular diseases: An umbrella review of systematic reviews and meta-analyses. J. Intern Med. 2022, 291(6), 779–800. [Google Scholar] [CrossRef] [PubMed]
- Rajagopalan, S.; Landrigan, P. Pollution and the Heart. N. Engl. J. Med. 2021, 385(20), 1881–1892. [Google Scholar] [CrossRef] [PubMed]
- Zhang, S.; Lu, W.; Wei, Z.; Zhang, H. Air Pollution and Cardiac Arrhythmias: From Epidemiological and Clinical Evidences to Cellular Electrophysiological Mechanisms. Front Cardiovasc Med. 2021, 8, 736151. [Google Scholar] [CrossRef] [PubMed]
- Pope, C.A.; Muhlestein, J.B.; Anderson, J.L.; Cannon, J.B.; Hales, N.M.; Meredith, K.G.; Le, V.; Horne, B.D. Short-Term Exposure to Fine Particulate Matter Air Pollution Is Preferentially Associated With the Risk of ST-Segment Elevation Acute Coronary Events. J. Am. Heart Assoc. 2015, 4(12), e002506. [Google Scholar] [CrossRef] [PubMed]
- Zhao, Y.; Chen, Y.; Liu, Y.; Tang, S.; Han, Y.; Zhuang, Y.; Fu, J.; Chang, Z.; Zhao, X.; Lei, J.; et al. Short-term exposure to ambient air pollution increased in-hospital non-ST-elevation myocardial infarction mortality risk, but not ST-elevation myocardial infarction: case-crossover based evidence from Beijing, China. Front Public Health 2025, 13, 1613082. [Google Scholar] [CrossRef] [PubMed]
- National Statistics Institute of Spain. Population by autonomous communities. Available online: https://www.ine.es/dynt3/inebase/en/index.htm?padre=523 (accessed on 3 June 2020).
- García-Lledó, A.; Rodríguez-Martín, S.; Tobías, A.; Alonso-Martín, J.; Ansede-Cascudo, J.C.; de Abajo, F.J. Heat waves, ambient temperature, and risk of myocardial infarction: an ecological study in the Community of Madrid. Rev. Esp. Cardiol. (Engl Ed) 2020, 73, 300–306. [Google Scholar] [CrossRef] [PubMed]
- Comunidad de Madrid. Atlas. Medio Ambiente en la Comunidad de Madrid. Capítulo 2. Medio Físico. Available online: http://www.madrid.org/cs/Satellite?blobcol=urldata&blobheader=application%2Fpdf&blobheadername1=Content-Disposition&blobheadervalue1=filename%3DCapitulo+2+medio+fisico+de+Atlas_Med_Amb-5.pdf&blobkey=id&blobtable=MungoBlobs&blobwhere=1158609635880&ssbinary=true (accessed on 21 May 2019).
- Montero, J.C.; Mirón, I.J.; Dıíaz, J.; Alberdi, J.C. The influence of environmental variables on mortality due to respiratory and cardiovascular diseases among the elderly in the Madrid region, Spain. Gac. Sanit. 1997, 11, 164–170. [Google Scholar] [CrossRef] [PubMed]
- Red de Calidad del Aire de la Comunidad de Madrid. Descripción de la red. (Community of Madrid Air Quality Network. Description of the network). Available online: https://gestiona.comunidad.madrid/azul_internet/html/web/3.htm?ESTADO_MENU=3 (accessed on 21 May 2025).
- Red de Calidad del Aire del Ayuntamiento de Madrid. Descripción de la red. (Madrid City Council Air Quality Network. Description of the network). Available online: https://airedemadrid.madrid.es/portales/calidadaire/es/En-portada/Red-de-estaciones-de-vigilancia-de-calidad-del-aire/?vgnextfmt=default&vgnextoid=aeca16d591bbf710VgnVCM2000001f4a900aRCRD&vgnextchannel=eb2e471c5c503710VgnVCM1000008a4a900aRCRD (accessed on 21 May 2025).
- Red de Calidad del Aire del Ayuntamiento de Madrid. Bases de datos. (Madrid City Council Air Quality Network. Databases). Available online: https://airedemadrid.madrid.es/portales/calidadaire/es/Bases-de-datos-y-publicaciones/Bases-de-datos-de-calidad-del-aire/?vgnextfmt=default&vgnextchannel=49be471c5c503710VgnVCM1000008a4a900aRCRD (accessed on 21 May 2025).
- World Health Organization. WHO global air quality guidelines: particulate matter (PM2.5 and PM10), ozone, nitrogen dioxide, sulfur dioxide and carbon monoxide; WHO: Geneva, 2021; Available online: https://www.who.int/publications/i/item/9789240034228 (accessed on 15 June 2025).
- Panigrahi, N. Inverse Distance Weight. In Encyclopedia of Mathematical Geosciences. Encyclopedia of Earth Sciences Series.; Daya Sagar, B.S., Cheng, Q., McKinley, J., Agterberg, F., Eds.; Springer: Cham, 2023. [Google Scholar] [CrossRef]
- Tobias, A.; Kim, Y.; Madaniyazi, L. Time-stratified case-crossover studies for aggregated data in environmental epidemiology: a tutorial. Int. J. Epidemiol. 2024, 53(2), dyae020. [Google Scholar] [CrossRef] [PubMed]
- Witte, D.R.; Grobbee, D.E.; Bots, M.L.; Hoes, A.W. A meta-analysis of excess cardiac mortality on Monday. Eur. J. Epidemiol. 2005, 20(5), 401–406. [Google Scholar] [CrossRef] [PubMed]
- Statistics Institute of the Autonomous Community of Madrid. Classification of geographic areas. chromeexten-si-on://efaidnbmnnnibpcajpcglclefindmkaj/https://web.comunidad.madrid/iestadis/fijas/estructu/economicas/cuentas/descarga/rmb01clas_geografica.pdf. Accessed 27 May 2025.
- Gasparrini, A.; Guo, Y.; Hashizume, M.; Lavigne, E.; Zanobetti, A.; Schwartz, J.; Tobias, A.; Tong, S.; Rocklöv, J.; Forsberg, B.; et al. Mortality risk attributable to high and low ambient temperature: a multicountry observational study. Lancet 2015, 386(9991), 369–375. [Google Scholar] [CrossRef] [PubMed]
- Gerber, Y.; Jacobsen, S.J.; Killian, J.M.; Weston, S.A.; Roger, V.L. Seasonality and daily weather conditions in relation to myocardial infarction and sudden cardiac death in Olmsted County, Minnesota, 1979 to 2002. J. Am. Coll. Cardiol. 2006, 48(2), 287–92. [Google Scholar] [CrossRef] [PubMed]
- Bhaskaran, K.; Hajat, S.; Haines, A.; Herrett, E.; Wilkinson, P.; Smeeth, L. Effects of ambient temperature on the incidence of myocardial infarction. Heart 2009, 95(21), 1760–9. [Google Scholar] [CrossRef] [PubMed]
- Lin, S.; Soim, A.; Gleason, K.A.; Hwang, S.A. Association Between Low Temperature During Winter Season and Hospitalizations for Ischemic Heart Diseases in New York State. J. Environ. Health 2016, 78(6), 66–74. [Google Scholar] [PubMed]
- You, Y.; Chen, J.; Wang, K.; Wu, T.; Bai, L.; Li, G.; Wu, S. Impact of Short-Term Exposure to Ozone on Hospital Admissions for Multiple Cardiovascular Diseases: A Systematic Review and Meta-Analysis. J. Am. Heart Assoc. 2025, 14(17), e037205. [Google Scholar] [CrossRef] [PubMed]
- Wu, K.; Ho, H.C.; Su, H.; Huang, C.; Zheng, H.; Zhang, W.; Tao, J.; Hossain, M.Z.; Zhang, Y.; Hu, K.; et al. A systematic review and meta-analysis of intraday effects of ambient air pollution and temperature on cardiorespiratory morbidities: First few hours of exposure matters to life. EBioMedicine 2022, 86, 104327. [Google Scholar] [CrossRef] [PubMed]
- Strobl, K.; Irfan, S.A.; Masood, H.; Latif, N.; Kurmi, O. Association between PM10 exposure and risk of myocardial infarction in adults: A systematic review and meta-analysis. PLoS ONE 2024, 19(5), e0301374. [Google Scholar] [CrossRef] [PubMed]
- Alexeeff, S.E.; Liao, N.S.; Liu, X.; Van Den Eeden, S.K.; Sidney, S. Long-Term PM2.5 Exposure and Risks of Ischemic Heart Disease and Stroke Events: Review and Meta-Analysis. J. Am. Heart Assoc. 2021, 10(1), e016890. [Google Scholar] [CrossRef] [PubMed]
- Campuzano, R.; Núñez, J.; Sánchez, V.; Gómez-Doblas, J.J.; Arrarte, V.; Cequier, Á.; Miranda, B.; Fernández, C.; Prado, N.; Rosillo, N.; et al. Impact of fine particulate matter (PM2.5) pollution on hospital admissions and mortality due to acute myocardial infarction in Spain. Rev. Esp. Cardiol. (Engl Ed) 2026, 79(2), 117–127. [Google Scholar] [CrossRef] [PubMed]
- Janssen, N.A.; Yang, A.; Strak, M.; Steenhof, M.; Hellack, B.; Gerlofs-Nijland, M.E.; Kuhlbusch, T.; Kelly, F.; Harrison, R.; Brunekreef, B.; et al. Oxidative potential of particulate matter collected at sites with different source characteristics. Sci. Total Environ. 2014, 472, 572–581. [Google Scholar] [CrossRef] [PubMed]
- Yang, Y.; Ruan, Z.; Wang, X.; Yang, Y.; Mason, T.G.; Lin, H.; Tian, L. Short-term and long-term exposures to fine particulate matter constituents and health: A systematic review and meta-analysis. Environ. Pollut. 2019, 247, 874–882. [Google Scholar] [CrossRef] [PubMed]
- Weichenthal, S.; Lavigne, E.; Evans, G.; Pollitt, K.; Burnett, R.T. Ambient PM2.5 and risk of emergency room visits for myocardial infarction: impact of regional PM2.5 oxidative potential: a case-crossover study. Environ. Health 2016, 15, 46. [Google Scholar] [CrossRef] [PubMed]
- García-Lledó, A.; García-de-Santiago, E. Direct and indirect influences of the environment on cardiovascular disease. Emergencias 2021, 33(6), 409–410. [Google Scholar] [CrossRef]
- Chen, R.; Jiang, Y.; Hu, J.; Chen, H.; Li, H.; Meng, X.; Ji, J.S.; Gao, Y.; Wang, W.; Liu, C.; et al. Hourly Air Pollutants and Acute Coronary Syndrome Onset in 1.29 Million Patients. Circulation 2022, 145(24), 1749–1760. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Correlation matrix for all pollutants, minimum temperature and minimum pressure. Correlations are calculated as pairwise Pearson’s correlation coefficients. Min=Minimum, SO2=Sulfur dioxide, CO=Carbon monoxide, NO2=Nitrogen dioxide, PM2.5=Particulate matter ≤2.5 μm, PM10=Particulate matter ≤10μm, O3=Ozone.
Figure 1.
Correlation matrix for all pollutants, minimum temperature and minimum pressure. Correlations are calculated as pairwise Pearson’s correlation coefficients. Min=Minimum, SO2=Sulfur dioxide, CO=Carbon monoxide, NO2=Nitrogen dioxide, PM2.5=Particulate matter ≤2.5 μm, PM10=Particulate matter ≤10μm, O3=Ozone.
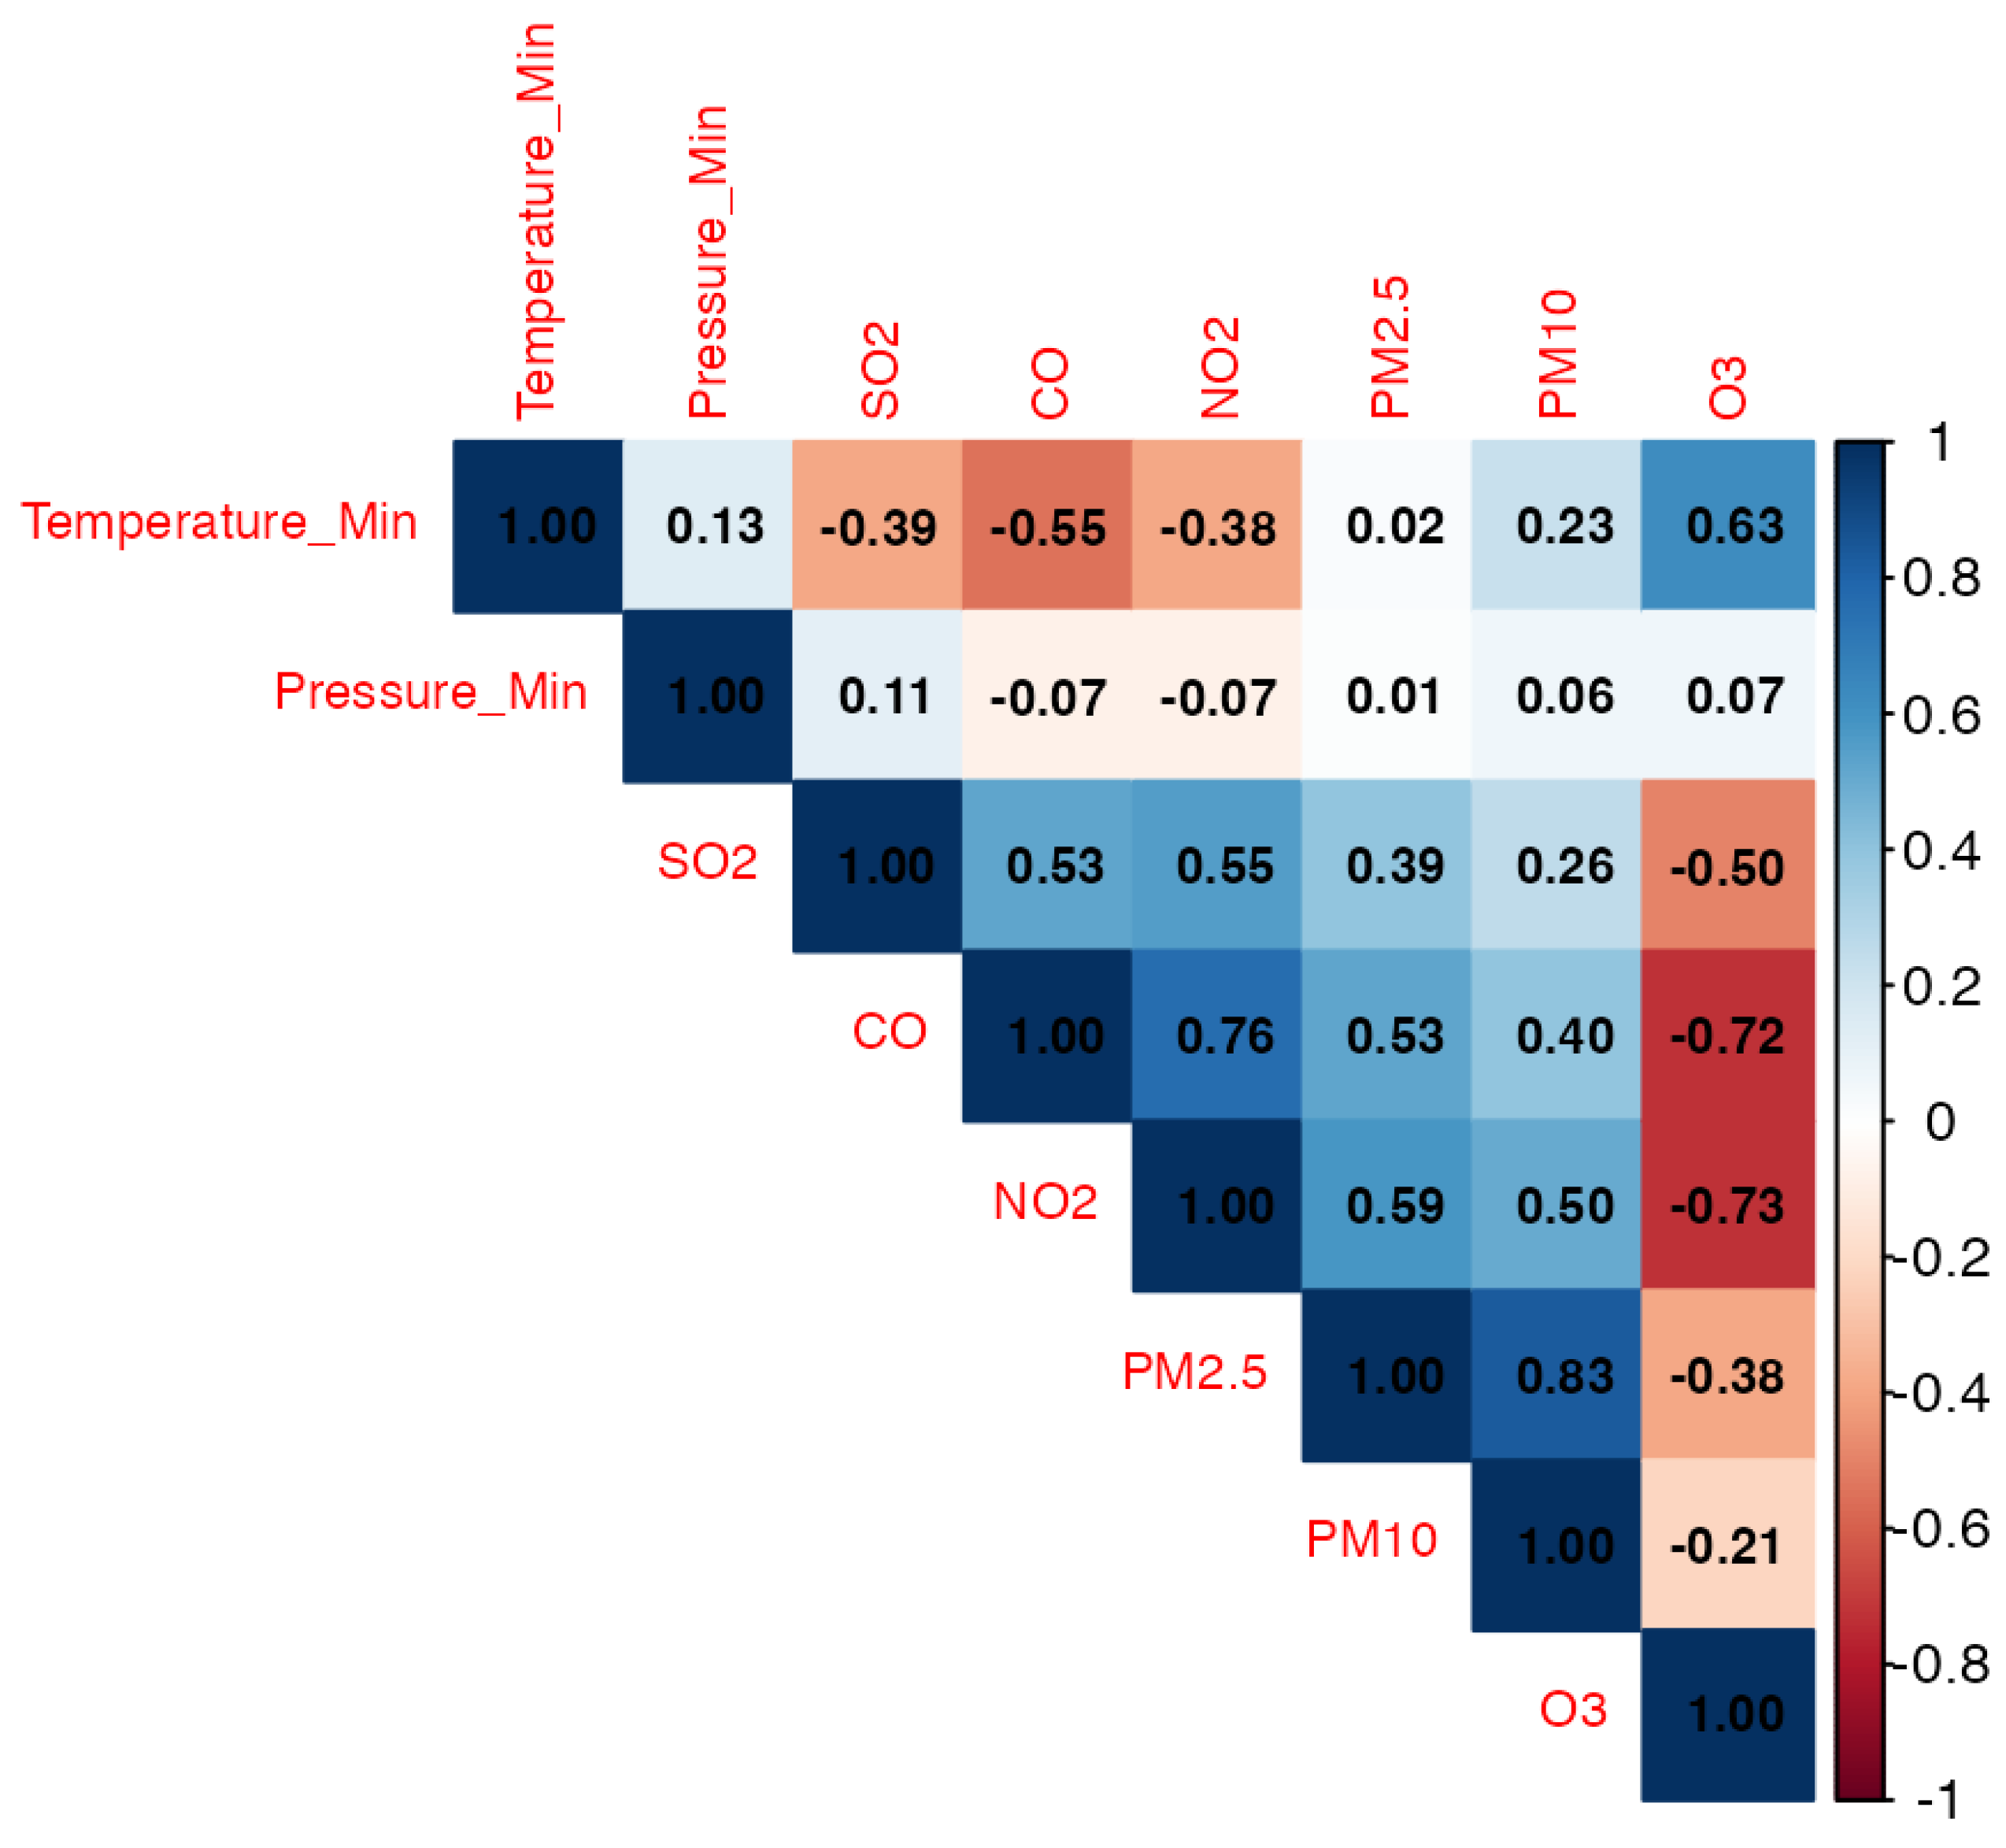

Table 1.
Summary of daily levels of pollution, daily minimum temperature and pressure, and daily number of CP-STEMI admissions in Madrid capital and all other 36 municipalities in the Metropolitan Area of Madrid.
Table 1.
Summary of daily levels of pollution, daily minimum temperature and pressure, and daily number of CP-STEMI admissions in Madrid capital and all other 36 municipalities in the Metropolitan Area of Madrid.
| All months | Winter (December-February) | Spring (March-May) | Summer (June-August) | Autumn (September-November) | ||
|---|---|---|---|---|---|---|
| Daily myocardial infarctions (N) | Madrid capital | 1.67 (1.42) | 1.88 (1.46) | 1.60 (1.39) | 1.49 (1.31) | 1.67 (1.49) |
| Other municipalities | 1.07 (1.14) | 1.27 (1.18) | 1.14 (1.15) | 0.89 (1.04) | 0.93 (1.13) | |
| Sulfur Dioxide (µg/m3) | Madrid capital | 7.23 (3.04); 0% |
8.04 (3.45); 0% |
6.29 (2.65); 0% |
7.41 (2.79); 0% |
7.29 (2.94); 0% |
| Other municipalities | 5.20 (1.72); 0% |
6.48 (2.08); 0% |
4.82 (1.30); 0% |
4.27 (0.85); 0% |
5.13 (1.54); 0% |
|
| Carbon monoxide (mg/m3) | Madrid capital | 0.38 (0.15); 0% |
0.47 (0.19); 0% |
0.34 (0.09); 0% |
0.28 (0.05); 0% |
0.42 (0.15); 0% |
| Other municipalities | 0.36 (0.12); 0% | 0.46 (0.14); 0% | 0.33 (0.07); 0% | 0.26 (0.03); 0% | 0.39 (0.11); 0% | |
| Nitrogen dioxide (µg/m3) | Madrid capital | 43.91 (16.29); 88.3% | 50.55 (17.86); 94.3% | 37.29 (12.84); 83.3% | 35.01 (11.05); 80.2% | 49.62 (16.18); 95.9% |
| Other municipalities | 31.86 (14.99); 59.0% | 40.47 (17.23); 74.8% | 26.02 (10.66); 46.5% | 22.87 (7.36); 38.9% | 38.39 (14.23); 77.0% | |
| Particulate matter≤2.5 (µg/m3) | Madrid capital | 10.51 (5.28); 16.3% | 11.46 (7.06); 26.4% | 8.57 (3.80); 6.7% | 10.78 (3.81); 11.4% | 11.59 (5.14); 21.7% |
| Other municipalities | 10.16 (4.86); 16.0% | 11.13 (6.30); 25.3% | 8.22 (3.40); 5.6% | 10.46 (3.76); 13.0% | 11.19 (4.81); 21.3% | |
| Particulate matter≤10 (µg/m3) | Madrid capital | 19.32 (10.10); 2.9% | 18.65 (11.47); 4.0% | 15.77 (8.06); 0.7% | 22.59 (8.96); 3.3% | 21.26 (10.31); 4.1% |
| Other municipalities | 19.82 (10.17); 3.4% | 19.18 (11.06); 4.0% | 16.01 (8.12); 1.0% | 23.00 (9.24); 4.0% | 22.17 (10.63); 4.9% | |
| Ozone (µg/m3) | Madrid capital | 43.88 (22.22) | 23.75 (14.57) | 51.57 (14.51) | 66.90 (14.45) | 34.11 (17.07) |
| Other municipalities | 53.52 (22.83) | 33.00 (17.39) | 63.70 (13.84) | 76.21 (11.93) | 41.40 (17.02) | |
| Minimum temp. (°C) | Getafe station* | 10.69 (7.04) | 3.07 (3.22) | 8.99 (4.11) | 19.37 (3.19) | 11.47 (4.69) |
| Minimum press. (hPa) | Getafe station* | 944.21 (6.38) | 946.80 (8.82) | 943.11 (5.53) | 943.26 (2.64) | 943.75 (6.34) |
Data for CP-STEMI are presented as mean (SD). All other data in each box are presented as the mean (SD) of the pollutant (up) and the proportion of days for which the level of the pollutant surpassed the acceptable limit (down) [15]. To estimate the mean and SD across the 36 municipalities surrounding Madrid capital, firstly the mean of measures was taken daily across the municipalities and then that mean measure was summarised. *Minimum daily temperature and pressure were taken from one meteorological station: Getafe.
Table 2.
Quasi-Poisson regression model coefficients for association with number of daily myocardial infarction admissions.
Table 2.
Quasi-Poisson regression model coefficients for association with number of daily myocardial infarction admissions.
| Coefficient | Model 1: Lag 0 | Model 2: Lag 1 | Model 3: Lag 2 | Model 4: Lag 3 | |||||
|---|---|---|---|---|---|---|---|---|---|
| aRR (95% CI) | P-value | aRR (95% CI) | P-value | aRR (95% CI) | P-value | aRR (95% CI) | P-value | ||
| Sulfur dioxide | 2nd tertile | 1.04 (0.94–1.14) | 0.447 | 1.03 (0.93–1.14) | 0.548 | 1.07 (0.97–1.17) | 0.202 | 1.08 (0.98–1.19) | 0.143 |
| 3rd tertile | 1.02 (0.92–1.14) | 0.707 | 1.00 (0.89–1.11) | 0.946 | 1.01 (0.90–1.13) | 0.891 | 0.99 (0.89–1.11) | 0.909 | |
| Carbon monoxide | 2nd tertile | 1.05 (0.96–1.14) | 0.312 | 1.04 (0.95–1.14) | 0.372 | 0.99 (0.90–1.09) | 0.863 | 0.90 (0.81–0.98) | 0.023 |
| 3rd tertile | 1.09 (0.98–1.22) | 0.129 | 1.02 (0.91–1.14) | 0.732 | 1.01 (0.90–1.14) | 0.834 | 1.00 (0.89–1.13) | 0.968 | |
| Nitrogen dioxide | 2nd tertile | 0.92 (0.85–1.01) | 0.067 | 0.94 (0.86–1.02) | 0.148 | 0.93 (0.86–1.02) | 0.116 | 0.93 (0.85–1.02) | 0.114 |
| 3rd tertile | 0.99 (0.89–1.09) | 0.778 | 1.01 (0.91–1.13) | 0.839 | 1.03 (0.92–1.15) | 0.662 | 1.02 (0.91–1.14) | 0.757 | |
| PM ≤ 2.5 µg/m3 | 2nd tertile | 0.96 (0.88–1.05) | 0.355 | 1.07 (0.98–1.17) | 0.143 | 1.10 (1.00–1.20) | 0.043 | 1.03 (0.95–1.13) | 0.462 |
| 3rd tertile | 1.00 (0.91–1.10) | 0.985 | 1.03 (0.93–1.13) | 0.624 | 1.08 (0.97–1.19) | 0.155 | 1.02 (0.92–1.14) | 0.645 | |
| PM ≤ 10 µg/m3 | 2nd tertile | 0.93 (0.85–1.01) | 0.095 | 1.01 (0.92–1.11) | 0.834 | 1.03 (0.93–1.13) | 0.600 | 1.00 (0.91–1.09) | 0.942 |
| 3rd tertile | 1.00 (0.90–1.10) | 0.938 | 1.02 (0.92–1.13) | 0.658 | 1.07 (0.96–1.19) | 0.217 | 1.02 (0.91–1.13) | 0.786 | |
| Ozone | 2nd tertile | 0.93 (0.85–1.01) | 0.095 | 1.01 (0.92–1.11) | 0.834 | 1.03 (0.93–1.13) | 0.600 | 1.00 (0.91–1.09) | 0.942 |
| 3rd tertile | 1.00 (0.90–1.10) | 0.938 | 1.02 (0.92–1.13) | 0.658 | 1.07 (0.96–1.19) | 0.217 | 1.02 (0.91–1.13) | 0.786 | |
| Minimum temp. (°C)* | 5°C increase | 0.891 (0.841-0.943) | <0.0001 | 0.877 (0.824-0.934) | <0.0001 | 0.865 (0.809-0.925) | <0.0001 | 0.856 (0.798-0.918) | <0.0001 |
| Minimum press. (hPa)* | 10 hPa increase | 0.997 (0.943-1.054) | 0.913 | 0.995 (0.938-1.056) | 0.867 | 0.995 (0.935-1.060) | 0.881 | 1.002 (0.937-1.071) | 0.962 |
aRR = adjusted rate ratio; CI=confidence interval. For the pollutants, the reference level is the 1st tertile. In these models, “Lag X” means that the main exposure was included in the model as the average of today’s measure and the previous X days’ measures was calculated. E.g. Lag 0 is just today’s measure, Lag 1 is the average of today and yesterday’s measure, etc. All models where the main exposure is the level of a pollutant are adjusted for day-of-week, month, year, minimum temperature and minimum pressure, and were conditioned on municipality. The adjustment variables of minimum temperature and minimum pressure are included in the models with the same number of lags as the main exposure. *The model with the meteorological measures includes both minimum temperature and minimum pressure and is adjusted for day-of-week, month and year. The aRRs are for a 5°C increase in minimum temperature and a 10 hPa increase in minimum pressure, respectively.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.