

Submitted:
11 November 2026
Posted:
12 November 2026
You are already at the latest version
Abstract
Background: Antifibrotic therapies slow disease progression in idiopathic pulmonary fibrosis (IPF) and are increasingly used in progressive pulmonary fibrosis (PPF), but adverse events may compromise treatment persistence. This study evaluated adverse events and treatment tolerability with pirfenidone and nintedanib in patients with IPF or PPF. Methods: This single-center ambidirectional study included 151 patients treated from January 2022 to June 2025 (120 retrospective; 31 prospective). Adverse events and treatment modifications were recorded. Results: Mean age was 67.5 ± 10.1 years; 64.9% were male, 68.9% had IPF, and 31.1% had PPF. At least one adverse event occurred in 56.3%, most commonly nausea (32.5%), vomiting (21.9%), and diarrhea (17.9%). Overall adverse-event rates were similar with pirfenidone and nintedanib (52.4% vs. 61.2%; p = 0.278). Diarrhea (6.0% vs. 32.8%; p < 0.001) and vomiting (15.5% vs. 29.9%; p = 0.034) were more frequent with nintedanib, whereas photosensitivity was more frequent with pirfenidone (16.7% vs. 1.5%; p = 0.002). Diabetes mellitus was associated with adverse events (74.1% vs. 52.4%; p = 0.040). Permanent treatment discontinuation occurred in 7.9%. Conclusions: Adverse events were common but generally manageable. The agents showed distinct adverse-event profiles, supporting early, individualized monitoring to acilitate treatment continuation.
Keywords:
adverse events
; antifibrotic therapy
; idiopathic pulmonary fibrosis
; nintedanib
; pirfenidone
; progressive pulmonary fibrosis
; real-world data
1. Introduction
Interstitial lung diseases (ILDs) comprise a heterogeneous group of disorders characterized by varying degrees of inflammation, fibrosis, and structural remodeling of the lung parenchyma. ILDs represent an important and increasingly recognized field of respiratory medicine, with a substantial clinical and research burden also demonstrated in Türkiye [1,2]. Idiopathic pulmonary fibrosis (IPF) is a chronic, progressive fibrotic interstitial lung disease of unknown etiology, characterized by a usual interstitial pneumonia pattern on high-resolution computed tomography and/or histopathological examination [3,4]. IPF predominantly affects older adults and is associated with progressive deterioration in lung function, impaired quality of life, and poor survival [4]. Although IPF represents the prototypical progressive fibrotic ILD, progressive fibrosis may also develop in patients with other forms of ILD. The 2022 ATS/ERS/JRS/ALAT clinical practice guideline defined progressive pulmonary fibrosis (PPF) in patients with fibrotic ILD other than IPF as the presence of at least two of three criteria—worsening respiratory symptoms, physiological evidence of disease progression, and radiological evidence of disease progression—occurring within the previous year without an alternative explanation [3]. This concept has expanded the clinical framework of progressive fibrotic lung disease beyond IPF and has increased interest in antifibrotic treatment across a broader spectrum of patients. Pirfenidone and nintedanib are established antifibrotic therapies for IPF. Randomized clinical trials have demonstrated that antifibrotic therapy reduces the rate of decline in forced vital capacity and slows disease progression in patients with IPF [5,6,7]. Evidence supporting antifibrotic treatment has also extended to progressive fibrotic ILDs other than IPF [3,8]. Despite their established efficacy, long-term use of antifibrotic agents is frequently complicated by adverse events. Gastrointestinal adverse events are particularly common, with diarrhea frequently associated with nintedanib and nausea and other gastrointestinal symptoms occurring with pirfenidone. Hepatic laboratory abnormalities and photosensitivity reactions may also occur [9,10,11,12]. These adverse events may necessitate supportive treatment, dose reduction, temporary treatment interruption, switching between antifibrotic agents, or permanent treatment discontinuation. Randomized controlled trials provide essential evidence regarding efficacy and safety; however, patients encountered in routine clinical practice may differ from trial populations with respect to age, comorbidity burden, disease phenotype, and treatment duration. Real-world studies are therefore valuable for characterizing treatment tolerability [9,10,11,12,13]. Therefore, this study aimed to evaluate the frequency and pattern of adverse events associated with pirfenidone and nintedanib in patients with IPF and PPF in a real-world clinical setting. We also investigated clinical factors associated with adverse events and compared the safety and tolerability profiles of the two antifibrotic agents.
2. Materials and Methods
2.1. Study Design and Setting
This single-center, ambidirectional observational study was conducted at the Department of Pulmonology, İnönü University Turgut Özal Medical Center, Malatya, Türkiye. Patients who were evaluated at the pulmonology outpatient clinic between 1 January 2022 and 1 June 2025 were screened for eligibility. The study protocol was approved by the İnönü University Scientific Research Ethics Committee (approval no. 2025/6708).
2.2. Study Population
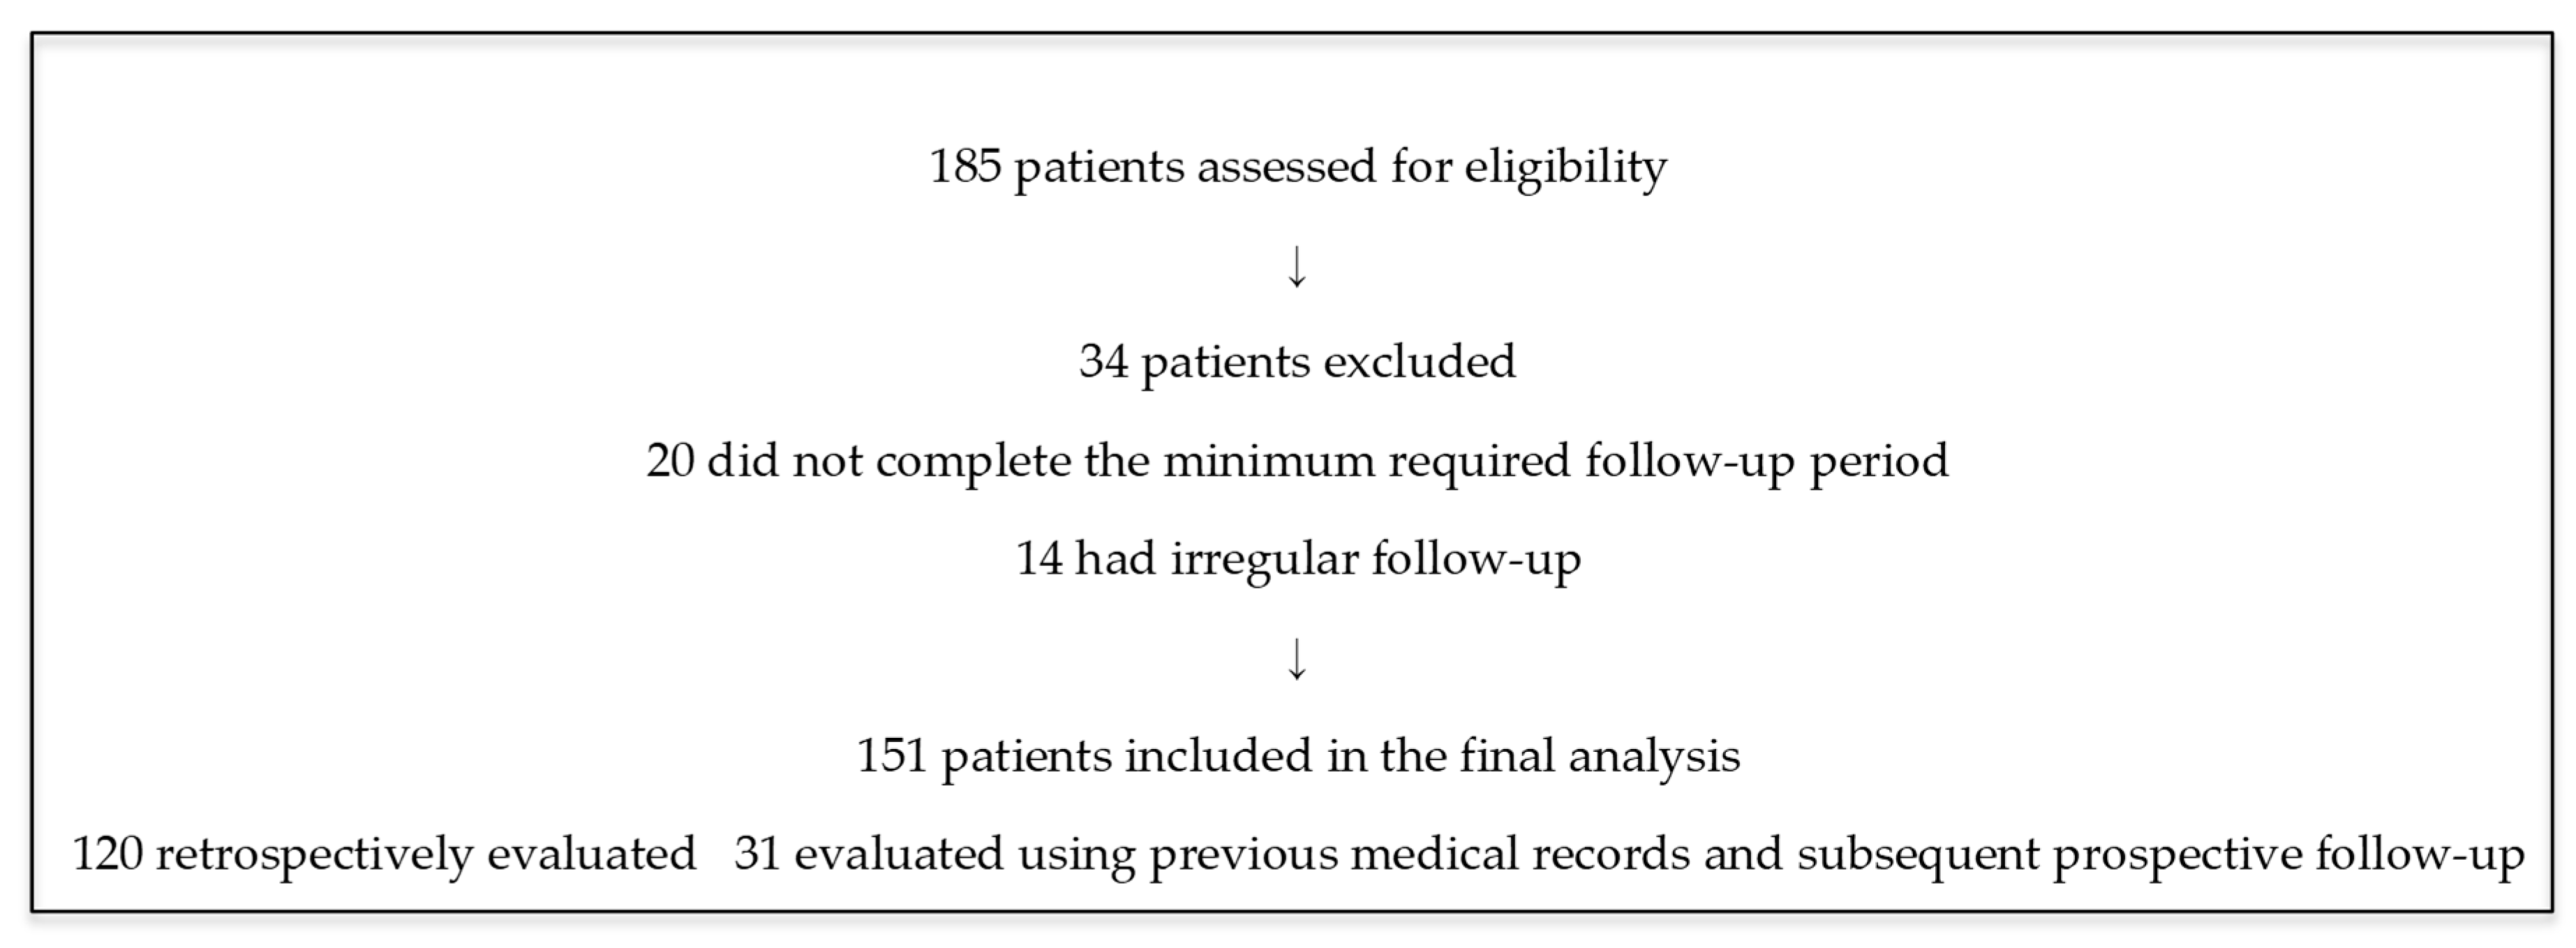
A total of 185 patients who presented with a diagnosis or suspicion of ILD, were subsequently diagnosed with IPF or PPF, and received antifibrotic treatment with pirfenidone or nintedanib were screened for eligibility. Of these, 34 patients were excluded: 20 because they did not complete the minimum required follow-up period and 14 because of irregular follow-up. Consequently, 151 patients were included in the final analysis. Of these, 120 patients were evaluated retrospectively, while 31 patients were evaluated using their previous medical records and subsequent prospective follow-up.
2.3. Eligibility Criteria
Patients were eligible for inclusion if they were aged >18 years, had a minimum follow-up duration of 6 months with regular clinical visits, and were able to perform spirometric testing. Patients who discontinued follow-up before completing the minimum required follow-up period or who did not attend regular follow-up visits were excluded.
2.4. Data Collection and Clinical Variables
Patient data were obtained from the Hospital Management Information System of İnönü University Turgut Özal Medical Center, including outpatient clinical records and hospitalization discharge summaries. Demographic and clinical variables included age, sex, body mass index (BMI), smoking status, comorbidities, type of ILD, pulmonary function test parameters, including spirometric measurements and diffusing capacity of the lungs for carbon monoxide (DLCO), and echocardiographic findings. Treatment-related variables included the antifibrotic agent used (pirfenidone or nintedanib), adverse events occurring during antifibrotic therapy, treatment modifications, treatment discontinuation, and requirement for hospitalization.
2.5. Assessment of Antifibrotic Treatment and Adverse Events
Patients receiving pirfenidone or nintedanib were evaluated for adverse events occurring during antifibrotic therapy. For retrospectively evaluated patients, adverse events were identified from outpatient clinic records and documented medical data. For prospectively followed patients, adverse events were assessed through direct questioning during follow-up visits. Recorded adverse events included gastrointestinal symptoms, such as nausea, vomiting, diarrhea, and dyspepsia, as well as liver function test abnormalities, photosensitivity, allergic reactions, pruritus, electrolyte abnormalities, and headache. A liver function test abnormality was defined as a value exceeding the upper limit of the reference range. Treatment-related modifications, including dose reduction, temporary treatment interruption, switching between antifibrotic agents, and permanent treatment discontinuation, were also recorded.
2.6. Outcomes
The primary outcome was the occurrence of at least one adverse event during antifibrotic treatment. Secondary outcomes included the type and timing of adverse events; comparison of adverse-event profiles between pirfenidone and nintedanib; treatment modifications related to tolerability; and identification of demographic and clinical factors associated with adverse events.
2.7. Statistical Analysis
Statistical analyses were performed using SPSS version 22.0 (SPSS Inc., Chicago, IL, USA). Categorical variables were expressed as numbers and percentages, whereas continuous variables were presented as mean ± standard deviation. The normality of continuous variables was assessed using the Kolmogorov–Smirnov test. Categorical variables were compared between groups using Pearson’s chi-square test or Fisher’s exact test, as appropriate, based on expected cell counts. Student’s t-test was used for comparisons of continuous variables between two groups. A two-sided p-value < 0.05 was considered statistically significant.
2.8. Ethical Considerations
The study was approved by the İnönü University Scientific Research Ethics Committee (approval no. 2025/6708). Informed consent was obtained from prospectively followed participants. The requirement for informed consent was waived for the retrospective component of the study due to its retrospective nature.
Figure 1.
Patient Selection Flowchart.
3. Results
3.1. Baseline Characteristics
A total of 151 patients were included in the study. Of these, 98 (64.9%) were male and 53 (35.1%) were female. The mean age was 67.5 ± 10.1 years, and the mean BMI was 27.7 ± 4.5 kg/m². The mean forced vital capacity (FVC) was 2482.1 ± 855.6 mL, corresponding to 79.2 ± 20.8% of the predicted value. The mean FEV1/FVC ratio was 82.9 ± 7.3%, and the mean DLCO was 61.2 ± 20.1% of the predicted value. A history of smoking was present in 95 patients (62.9%). The most frequent comorbidities were hypertension (43.0%), chronic lung disease (36.4%), coronary artery disease (26.5%), diabetes mellitus (17.9%), malignancy (9.9%), heart failure (6.0%), chronic kidney disease (3.3%), and pulmonary hypertension (3.3%). IPF was diagnosed in 104 patients (68.9%) and PPF in 47 (31.1%). Among patients with PPF, 76.6% had connective tissue disease-associated ILD, 17.0% had hypersensitivity pneumonitis, 4.3% had sarcoidosis, and 2.1% had other diagnoses.
3.2. Antifibrotic Treatment Characteristics
Pirfenidone was used in 84 patients (55.6%), whereas 67 patients (44.4%) received nintedanib. Full-dose treatment was maintained in 89 patients (58.9%), while 62 (41.1%) received a reduced dose. Switching between antifibrotic agents occurred in 25 patients (16.6%), and permanent treatment discontinuation occurred in 12 (7.9%). Regarding follow-up duration, 59 patients (39.1%) were followed for 6–12 months, 51 (33.8%) for 12–24 months, and 41 (27.2%) for more than 24 months.
3.3. Adverse Events During Antifibrotic Therapy
At least one adverse event occurred in 85 of 151 patients (56.3%). The most frequent adverse events were nausea (32.5%), vomiting (21.9%), diarrhea (17.9%), photosensitivity (9.9%), pruritus (9.9%), liver function test abnormalities (7.9%), headache (5.3%), and dyspepsia (4.0%). Allergic reactions and electrolyte abnormalities were each observed in 1.3% of patients. Among patients who experienced adverse events, 17.6% developed their first adverse event within the first month of treatment, 47.1% between 1 and 3 months, 18.8% between 3 and 6 months, 10.6% between 6 and 12 months, and 5.9% after 12 months. Temporary treatment interruption due to adverse events was required in 31 patients (20.5%), whereas hospitalization due to adverse events occurred in five patients (3.3%).
3.4. Factors Associated with Adverse Events
The occurrence of at least one adverse event was significantly more frequent among patients with diabetes mellitus than among those without diabetes (74.1% vs. 52.4%, p = 0.040). No statistically significant association with the overall occurrence of adverse events was observed for sex, age, BMI, smoking status, hypertension, chronic lung disease, coronary artery disease, heart failure, chronic kidney disease, pulmonary hypertension, malignancy, antifibrotic agent, or IPF versus PPF diagnosis.
3.5. Specific Adverse Events and Associated Clinical Factors
Nausea was significantly more frequent among women than men (47.2% vs. 24.5%, p = 0.004). Similarly, vomiting occurred more frequently among women (37.7% vs. 13.3%, p = 0.001). Diarrhea was more frequent among patients with PPF than among those with IPF (29.8% vs. 12.5%, p = 0.010), whereas photosensitivity was more frequent in patients with IPF than in those with PPF (13.5% vs. 2.1%, p = 0.038). The frequency of vomiting was significantly lower among patients with a history of smoking than among nonsmokers (15.8% vs. 32.1%, p = 0.019).
3.6. Comparison of Pirfenidone and Nintedanib
At least one adverse event occurred in 52.4% of patients receiving pirfenidone and 61.2% of those receiving nintedanib, with no statistically significant difference between the two groups (p = 0.278). Diarrhea was more frequent with nintedanib than with pirfenidone (32.8% vs. 6.0%, p < 0.001), as was vomiting (29.9% vs. 15.5%, p = 0.034). In contrast, photosensitivity was more frequent with pirfenidone (16.7% vs. 1.5%, p = 0.002). Liver function test abnormalities occurred in 4.8% of patients receiving pirfenidone and 11.9% of those receiving nintedanib; however, this difference was not statistically significant (p = 0.105). Permanent treatment discontinuation occurred in 9.5% of patients receiving pirfenidone and 6.0% of those receiving nintedanib, without a significant difference between the groups (p = 0.422).

Table 1.
Baseline Clinical Characteristics of the Study Population.
| Characteristic | Total (n = 151) |
| Age, years | 67.5 ± 10.1 |
| Male sex | 98 (64.9%) |
| Female sex | 53 (35.1%) |
| BMI, kg/m² | 27.7 ± 4.5 |
| Smoking history | 95 (62.9%) |
| FVC, mL | 2482.1 ± 855.6 |
| FVC, % predicted | 79.2 ± 20.8 |
| FEV1/FVC, % | 82.9 ± 7.3 |
| DLCO, % predicted | 61.2 ± 20.1 |
| Hypertension | 65 (43.0%) |
| Chronic lung disease | 55 (36.4%) |
| Coronary artery disease | 40 (26.5%) |
| Diabetes mellitus | 27 (17.9%) |
| Malignancy | 15 (9.9%) |
| Heart failure | 9 (6.0%) |
| Chronic kidney disease | 5 (3.3%) |
| Pulmonary hypertension | 5 (3.3%) |
| IPF | 104 (68.9%) |
| PPF | 47 (31.1%) |
Table 2.
Antifibrotic Treatment Characteristics and Adverse Events.
| Variable | n (%) |
| Pirfenidone | 84 (55.6) |
| Nintedanib | 67 (44.4) |
| Full-dose treatment | 89 (58.9) |
| Reduced-dose treatment | 62 (41.1) |
| Switching between antifibrotics | 25 (16.6) |
| Permanent treatment discontinuation | 12 (7.9) |
| ≥1 adverse event | 85 (56.3) |
| Nausea | 49 (32.5) |
| Vomiting | 33 (21.9) |
| Diarrhea | 27 (17.9) |
| Photosensitivity | 15 (9.9) |
| Pruritus | 15 (9.9) |
| Liver function test abnormality | 12 (7.9) |
| Headache | 8 (5.3) |
| Dyspepsia | 6 (4.0) |
| Allergic reaction | 2 (1.3) |
| Electrolyte abnormality | 2 (1.3) |
| Temporary treatment interruption | 31 (20.5) |
| Hospitalization due to adverse events | 5 (3.3) |
Table 3.
Factors Associated with the Occurrence of Adverse Events.
| Variable | Adverse Event | No Adverse Event | p-Value |
| Female | 34 (64.2%) | 19 (35.8%) | 0.152 |
| Male | 51 (52.0%) | 47 (48.0%) | |
| Age, years | 67.6 ± 9.8 | 67.4 ± 10.6 | 0.872 |
| BMI, kg/m² | 27.8 ± 4.5 | 27.6 ± 4.6 | 0.805 |
| Smoking history | 48 (50.5%) | 47 (49.5%) | 0.063 |
| No smoking history | 37 (66.1%) | 19 (33.9%) | |
| Diabetes mellitus | 20 (74.1%) | 7 (25.9%) | 0.040 |
| No diabetes mellitus | 65 (52.4%) | 59 (47.6%) | |
| Pirfenidone | 44 (52.4%) | 40 (47.6%) | 0.278 |
| Nintedanib | 41 (61.2%) | 26 (38.8%) | |
| IPF | 56 (53.8%) | 48 (46.2%) | 0.368 |
| PPF | 29 (61.7%) | 18 (38.3%) |
Table 4.
Comparison of Adverse Events between Pirfenidone and Nintedanib.
| Adverse Event | Pirfenidone (n = 84) | Nintedanib (n = 67) | p-Value |
| Any adverse event | 44 (52.4%) | 41 (61.2%) | 0.278 |
| Nausea | 25 (29.8%) | 24 (35.8%) | 0.429 |
| Vomiting | 13 (15.5%) | 20 (29.9%) | 0.034 |
| Diarrhea | 5 (6.0%) | 22 (32.8%) | <0.001 |
| Dyspepsia | 5 (6.0%) | 1 (1.5%) | 0.227 |
| Liver function test abnormality | 4 (4.8%) | 8 (11.9%) | 0.105 |
| Photosensitivity | 14 (16.7%) | 1 (1.5%) | 0.002 |
| Allergic reaction | 2 (2.4%) | 0 (0%) | 0.503 |
| Pruritus | 10 (11.9%) | 5 (7.5%) | 0.365 |
| Electrolyte abnormality | 2 (2.4%) | 0 (0%) | 0.503 |
| Headache | 3 (3.6%) | 5 (7.5%) | 0.467 |
4. Discussion
In this real-world study of patients with IPF and PPF receiving antifibrotic therapy, more than half of the patients experienced at least one adverse event, with gastrointestinal events representing the predominant safety concern. Although the overall frequency of adverse events did not significantly differ between pirfenidone and nintedanib, the profiles of individual adverse events differed between the two agents. Diarrhea and vomiting were more frequent with nintedanib, whereas photosensitivity was more frequent with pirfenidone. Liver function test abnormalities occurred with both treatments without a statistically significant between-group difference. Diabetes mellitus was associated with a higher overall frequency of adverse events, while nausea and vomiting were more frequent among women.
At least one adverse event was observed in 56.3% of our study population. Gastrointestinal events predominated, with nausea, vomiting, and diarrhea occurring in 32.5%, 21.9%, and 17.9% of patients, respectively. These findings are consistent with previous randomized trials and real-world studies demonstrating that gastrointestinal intolerance constitutes one of the major challenges during long-term antifibrotic therapy. Galli et al. reported a substantial burden of adverse drug reactions with both pirfenidone and nintedanib in routine clinical practice, while the systematic review and meta-analysis by Finnerty et al. similarly identified gastrointestinal adverse events as a major component of the safety profiles of antifibrotic agents [9,14]. Pharmacovigilance data reported by Sun et al. further demonstrated distinct but overlapping adverse-event profiles for pirfenidone and nintedanib [10]. Notably, adverse events in our study tended to occur early after treatment initiation. Approximately two-thirds of adverse events occurred within the first 3 months. This finding highlights the potential clinical value of closer monitoring during the early phase of antifibrotic treatment.
Although the overall frequency of adverse events was numerically higher with nintedanib than with pirfenidone (61.2% vs. 52.4%), the difference was not statistically significant (p = 0.278). In contrast, diarrhea and vomiting were more frequent with nintedanib, whereas photosensitivity was more frequent with pirfenidone. These findings are broadly consistent with established safety profiles reported in real-world cohorts, systematic reviews, and pharmacovigilance studies [9,10,11,12,14]. Importantly, our findings do not indicate superiority of either drug with respect to overall tolerability; rather, they suggest that the two agents have different patterns of adverse events.
Liver function test abnormalities were observed in 7.9% of the overall study population. Although the frequency was numerically higher among patients receiving nintedanib than among those receiving pirfenidone (11.9% vs. 4.8%), the difference was not statistically significant (p = 0.105). Previous real-world and pharmacovigilance studies have demonstrated that hepatic laboratory abnormalities may occur during treatment with both antifibrotic agents [9,10,11,12]. Because of the relatively small number of events in our cohort, the numerical difference between the two agents should be interpreted cautiously.
Diabetes mellitus was associated with a significantly higher overall frequency of adverse events (74.1% vs. 52.4%, p = 0.040). Because our analyses were primarily univariable and the number of patients with diabetes was limited, diabetes should not be interpreted as an independent predictor of adverse events. Sex-related differences were also observed for individual gastrointestinal adverse events. Nausea and vomiting were more frequent among women. Previous pharmacovigilance data have also described sex differences in reported adverse drug reactions [15]. However, sex was not significantly associated with the occurrence of any adverse event overall in our cohort.
In our study, the frequency of vomiting was significantly lower among patients with a history of smoking than among nonsmokers (15.8% vs. 32.1%, p = 0.019). Although this finding may appear counterintuitive, previous literature has suggested that nicotine may modulate pathways involved in nausea and vomiting [16]. Nevertheless, given the observational nature of our study and the absence of adjustment for potential confounders, this finding should be interpreted cautiously and should not be considered evidence of a protective effect of smoking.
Although adverse events were common, permanent treatment discontinuation occurred in only 7.9% of patients. Dose reduction was required in 41.1%, temporary treatment interruption in 20.5%, and switching between antifibrotic agents in 16.6%. Real-world experience indicates that treatment modification and switching may be used when tolerability problems occur [11,12,13,17]. However, given the observational design of our study, it cannot be concluded that these interventions themselves caused improved treatment persistence.
Adverse events were common but hospitalization due to adverse events was uncommon, occurring in only 3.3% of patients, and fewer than one in ten patients permanently discontinued antifibrotic treatment. The concentration of adverse events during the early months of therapy suggests that closer surveillance during this period may be useful.
This study has several strengths, including the evaluation of both IPF and PPF populations, the inclusion of patients treated with both established antifibrotic agents, and the assessment of treatment modifications in addition to individual adverse events, thereby reflecting routine clinical practice. However, several limitations should be acknowledged. First, this was a single-center study with a relatively limited sample size. Second, the ambidirectional design resulted in different methods of adverse-event ascertainment, potentially introducing information and ascertainment bias. Third, adverse events were not graded using a standardized severity classification system. Fourth, some subgroup analyses included small numbers of patients. Finally, the analyses were primarily univariable, and potential confounding factors could not be fully accounted for.
5. Conclusions
In this real-world cohort of patients with IPF and PPF, adverse events during antifibrotic therapy were common but were generally manageable. Gastrointestinal adverse events were the most frequently observed events and occurred predominantly during the early months of treatment. Although the overall frequency of adverse events did not significantly differ between pirfenidone and nintedanib, their adverse-event profiles differed, with diarrhea and vomiting being more frequent with nintedanib and photosensitivity being more frequent with pirfenidone. Diabetes mellitus was associated with a higher overall frequency of adverse events, while nausea and vomiting were more frequent among women. Despite the relatively high frequency of adverse events, permanent treatment discontinuation was uncommon. These findings highlight the importance of early and individualized monitoring and appropriate management of adverse events to support the continuation of antifibrotic therapy.
Author Contributions
Conceptualization, Y.E.E. and T.K.; Methodology, Y.E.E. and T.K.; Investigation, Y.E.E.; Data Curation, Y.E.E.; Writing—Original Draft Preparation, Y.E.E.; Writing—Review and Editing, Y.E.E. and T.K.; Supervision, T.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was approved by the İnönü University Scientific Research Ethics Committee (approval no. 2025/6708).
Informed Consent Statement
Informed consent was obtained from prospectively followed participants. The requirement for informed consent was waived for the retrospective component of the study due to its retrospective nature.
Data Availability Statement
The data supporting the findings of this study are available from the corresponding author upon reasonable request.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Musellim, B.; Okumus, G.; Uzaslan, E.; et al. Epidemiology and distribution of interstitial lung diseases in Turkey. Clin. Respir. J. 2014, 8(1), 55–62. [Google Scholar] [CrossRef] [PubMed]
- Aycicek, O.; Cetinkaya, E.; Demirci Ucsular, F.; Bayram, N.; Senyigit, A.; Aksel, N.; et al. Research burden of interstitial lung diseases in Turkey (RBILD). Sarcoidosis Vasc. Diffus. Lung Dis. 2022, 39(1), e2022006. [Google Scholar] [CrossRef] [PubMed]
- Raghu, G.; Remy-Jardin, M.; Richeldi, L.; et al. Idiopathic pulmonary fibrosis (an update) and progressive pulmonary fibrosis in adults: an official ATS/ERS/JRS/ALAT clinical practice guideline. Am. J. Respir. Crit. Care Med. 2022, 205(9), e18–e47. [Google Scholar] [CrossRef] [PubMed]
- Lederer, D.J.; Martinez, F.J. Idiopathic pulmonary fibrosis. N Engl. J. Med. 2018, 378(19), 1811–1823. [Google Scholar] [CrossRef] [PubMed]
- Noble, P.W.; Albera, C.; Bradford, W.Z.; et al. Pirfenidone in patients with idiopathic pulmonary fibrosis (CAPACITY): two randomised trials. Lancet 2011, 377(9779), 1760–1769. [Google Scholar] [CrossRef] [PubMed]
- King, T.E., Jr.; Bradford, W.Z.; Castro-Bernardini, S.; et al. A phase 3 trial of pirfenidone in patients with idiopathic pulmonary fibrosis. N Engl. J. Med. 2014, 370(22), 2083–2092. [Google Scholar] [CrossRef] [PubMed]
- Brown, K.K.; Flaherty, K.R.; Cottin, V.; et al. Lung function outcomes in the INPULSIS trials of nintedanib in idiopathic pulmonary fibrosis. Respir. Med. 2019, 146, 42–48. [Google Scholar] [CrossRef] [PubMed]
- Ghazipura, M.; Mammen, M.J.; Bissell, B.D.; et al. Pirfenidone in progressive pulmonary fibrosis: a systematic review and meta-analysis. Ann. Am. Thorac. Soc. 2022, 19(6), 1030–1039. [Google Scholar] [CrossRef] [PubMed]
- Galli, J.A.; Pandya, A.; Vega-Olivo, M.; Dass, C.; Zhao, H.; Criner, G.J. Pirfenidone and nintedanib for pulmonary fibrosis in clinical practice: tolerability and adverse drug reactions. Chest 2017, 152(1), 273–282. [Google Scholar]
- Sun, X.; Wang, H.; Zhan, X.; Yan, Y.; Chen, K.; An, Z.; et al. Comparison of the safety profiles for pirfenidone and nintedanib: a disproportionality analysis of the US FDA adverse event reporting system. Front Pharmacol. 2024, 15, 1256649. [Google Scholar] [CrossRef] [PubMed]
- Cameli, P.; Refini, R.M.; Bergantini, L.; et al. Long-term follow-up of patients with idiopathic pulmonary fibrosis treated with antifibrotic drugs: real-world experience. Front Mol. Biosci. 2020, 7, 581828. [Google Scholar] [PubMed]
- Kou, M.; Jiao, Y.; Li, Z.; Wei, B.; Li, Y.; Cai, Y.; et al. Real-world safety and efficacy of pirfenidone and nintedanib in idiopathic pulmonary fibrosis: a systematic review and meta-analysis. Eur. J. Clin. Pharmacol. 2024, 80(10), 1445–1460. [Google Scholar] [CrossRef] [PubMed]
- Cerri, S.; Monari, M.; Guerrieri, A.; et al. Real-life comparison of pirfenidone and nintedanib in patients with idiopathic pulmonary fibrosis: a 24-month assessment. Respir. Med. 2019, 159, 105803. [Google Scholar] [CrossRef] [PubMed]
- Finnerty, J.P.; Ponnuswamy, A.; Dutta, P.; et al. Antifibrotic drugs in idiopathic pulmonary fibrosis and progressive pulmonary fibrosis: a systematic review and meta-analysis. BMC Pulm. Med. 2021, 21(1), 411. [Google Scholar] [CrossRef] [PubMed]
- Yu, Y.; Chen, J.; Li, D.; Wang, L.; Wang, W.; Liu, H. Sex differences in adverse drug reactions reported to the FDA adverse event reporting system (FAERS). Sci. Rep. 2016, 6, 24955. [Google Scholar] [PubMed]
- Sanger, G.J.; Andrews, P.L.R. Treatment of nausea and vomiting: gaps in our knowledge. Auton. Neurosci. 2006, 129(1–2), 3–16. [Google Scholar] [CrossRef] [PubMed]
- Milger, K.; Kneidinger, N.; Neurohr, C.; et al. Switching to nintedanib after discontinuation of pirfenidone due to adverse events in idiopathic pulmonary fibrosis. Eur. Respir. J. 2015, 46(4), 1217–1221. [Google Scholar] [PubMed]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.