

Submitted:
09 October 2026
Posted:
10 October 2026
You are already at the latest version
Abstract
Background: Patients with dementia frequently present with multiple chronic conditions (MCCs). Growing evidence indicates these conditions do not co-occur by chance but may interact in ways that accelerate cognitive decline. In this study, we presented a machine-learning framework to identify these non-random, personalized MCC patterns associated with dementia, based on patients’ pre-existing conditions. Furthermore, we demonstrated a patient example illustrating how this approach enables the early detection of emerging MCC trajectories.
Methods: To address this challenge, we introduced a lazy decision tree (lazyDT-MCCPath) framework using National Alzheimer’s Coordinating Center data. For each patient, lazyDT-MCCPath dynamically fine-tunes its training distribution based on pre-existing conditions from the preceding 3-5 years, while remaining MCCs were used to predict dementia risk. The decision tree provides a transparent pathway showing which emerging MCCs were associated with higher dementia risk.
Results: Unlike traditional eager decision trees (eagerDT), which lacked sufficient training data for 17%-33% of patient profiles, lazyDT-MCCPath successfully modeled all profiles and achieved a 0.17 improvement in AUROC (0.66 vs. 0.83).
Conclusions: lazyDT-MCCPath effectively translates pre-existing MCC profiles into personalized dementia risk probabilities for emerging conditions, which may help clinicians prioritize MCCs to monitor more closely.
Keywords:
dementia
; multimorbidity
; explainable artificial intelligence
; decision trees
; longitudinal modeling
; risk stratification
1. Introduction
Dementia is one of the major causes of disability and mortality among older adults, progressively impairing memory, cognitive function, and the ability to perform daily activities. In the United States, dementia and other related dementia care was estimated to cost more than $384 billion in 2025 [1] due to long-term assistance required by affected individuals [2]. This burden is further complicated by multimorbidity. People with dementia are 2.7 times more likely than matched non-dementia individuals to have at least two chronic conditions, commonly referred to as multiple chronic conditions (MCCs) [3]. Conversely, the presence of MCCs has been associated with up to a 66% increase in incident dementia risk among adults aged 60 years and older [4,5,6].
MCCs alone, however, do not adequately distinguish which patients will subsequently develop dementia. Approximately 51% of adults aged 60 years or older live with MCCs [7], yet only a subset progresses to dementia. Previous studies have associated singular conditions, including hypercholesterolemia, stroke, diabetes, and osteoporosis, with dementia risk [6], and have identified cardiovascular, metabolic, musculoskeletal, and mental health MCC clusters associated with cognitive decline or dementia [4,5,8,9,10]. These findings establish an important relationship between multimorbidity and dementia but leave a crucial clinical question unresolved: given a patient’s existing MCC patterns, which additional MCCs, if they emerge, may place that patient on a higher-risk pathway toward dementia?
The association of an emerging MCC with dementia risk is unlikely to be uniform across patients because newly developing MCCs may collectively interact with pre-existing MCCs to influence cognitive decline. Growing evidence indicates that certain combinations of diseases can interact and increase dementia risk beyond the effect of single conditions [11,12,13,14]. For example, cardiometabolic multimorbidity has been associated with greater cognitive decline than individual cardiometabolic conditions [14], while inflammatory processes may interact with other diseases to further increase dementia risk [12,13]. Moreover, chronic conditions do not appear together randomly. Existing multimorbidity literature describes non-random co-occurrence of diseases as associative multimorbidity, and identified commonly reported non-random disease patterns, including cardiometabolic, neurological-metabolic, and musculoskeletal-cardiovascular disease clusters [15,16,17]. Vetrano et al. further showed that these patterns are dynamic: older adults may move across MCC clusters over time, and changes in cluster composition are associated with different clinical outcomes [18]. These findings provide an important foundation for identifying high-dementia-risk MCC pathways, because the patient’s existing conditions may shape how, when, and which conditions emerge and whether the resulting collective pattern is associated with greater dementia risk. Therefore, dementia risk should be evaluated not only by the number of conditions present, but also by how, which, and in what order emerging MCCs develop within the context of the patient’s pre-existing MCC profile.
In our previous study [19], we demonstrated that artificial intelligence/machine learning (AI/ML) models can learn informative MCC patterns associated with dementia. Specifically, we developed a multi-label XGBoost model that achieved an area under the receiver operating characteristic curve (AUROC) of 0.865 for dementia prediction using MCC indicators alone. The result indicated that MCC patterns contain substantial information about MCC progression and future dementia status [19]. However, the model did not identify the dementia-risk level of the patient-specific MCC combinations. To address this gap, we developed the lazy decision tree (lazyDT-MCCPath), a query-specific framework that constructs an individualized decision tree for each patient. lazyDT-MCCPath adapts the training data to the patient’s pre-existing MCC patterns by assigning greater influence to patients with more similar pre-existing MCCs while retaining information from partially similar patients. The resulting tree predicts dementia and represents combinations of eligible MCCs associated with different predicted dementia probabilities and, thus, indicates the dementia risk level of the MCC combination. In sum, we combine established methods, including sample weighting, lazy machine-learning prediction, and a transparent decision tree, to develop lazyDT-MCCPath to visualize emerging MCCs and their contribution to the risk of dementia.
The primary objective of this study was to identify individualized MCC pathways to dementia. Specifically, lazyDT-MCCPath will identify which new MCCs, when they emerged during follow-up, were associated with higher predicted dementia risk for patients with specific pre-existing MCC profiles. We evaluated lazyDT-MCCPath over 3-, 4-, and 5-year follow-up periods and compared it with a regular decision tree (also called an eager decision tree – eagerDT). These pathways may help clinicians identify which emerging conditions contributing to dementia risk should be closely monitored or managed earlier, especially when the conditions are potentially modifiable.
2. Materials and Methods
2.1. Data Source
We conducted a retrospective longitudinal study using Version 3 of the Uniform Data Set (UDS) maintained by the National Alzheimer’s Coordinating Center (NACC) [20]. NACC collects participants’ visit-related survey data from 30+ National Institute on Aging–funded Alzheimer’s Disease Research Centers across the United States since 2005. The UDS includes longitudinal information on participant demographics, medical history, medication use, clinician-assessed diagnoses, cognitive status, and functional assessments. The data source and general cohort framework were consistent with those used in our previous study [19].
2.2. Cohort Selection
We included participants with at least two visits recorded under UDS Version 3 and excluded participants who died during follow-up. We chose Version 3 because it contains Form D2: Clinician-assessed Medical Conditions, a major source for our MCCs identification. Participants with dementia at their first eligible visit were also excluded because they did not provide an observable period during which changes in MCCs preceding dementia could be evaluated. For participants who developed dementia during follow-up, observations after the first documented dementia diagnosis were not included.
2.3. Study Design
Recall that our goal is to identify emerging MCCs associated with high dementia risk based on one’s pre-existing MCCs. To do that, we collected data from 3 time points: anchor (t2), pre-anchor (t1), and baseline (t0) (Figure 1), and we discuss their functions in detail below. Briefly, t2 defines the dementia label, t1 identifies the MCC predictors for dementia risk, and t0 identifies the patient’s pre-existing MCCs. We then used the patient’s pre-existing MCCs to fine-tune the training data distribution and used MCC predictors to develop the individualized prediction model, lazyDT-MCCPath.
We aligned each patient’s longitudinal record to an anchor visit, which served as the outcome assessment point. The anchor visit (t2) was defined as the first visit at which dementia was documented for patients who developed dementia or their last available NACC visit for patients who remained free of dementia. Dementia status was defined at the anchor visit. MCC information recorded at the anchor was not used as a predictor because conditions documented concurrently with the outcome could not be interpreted as preceding dementia-related signals.
The pre-anchor visit (t1) is defined as the visit immediately preceding the anchor visit (t2). It is used to capture MCCs that emerged before dementia diagnosis (t2) but after the baseline visit (t0). For patients who developed dementia, this represented the latest available clinical profile before the first documented dementia diagnosis; for patients who remained free of dementia, it represented their clinical profile immediately preceding their last available follow-up visit.
The baseline visit (t0) is defined as the visit 3-5 years before the anchor visit (t2). In this study, we used 3-, 4-, or 5-year periods prior to the anchor visit (t2) as an example. These periods were selected to capture long-term changes in multimorbidity while balancing the time required for MCC accumulation and dementia development against increasing loss to follow-up over longer periods. For each follow-up period, a follow-up-specific baseline visit (t0) was selected as the visit closest to 3, 4, or 5 years before the anchor (t2) within a ±180-day window. The eligible baseline windows were 915-1,275 days before the anchor (t2) for the 3-year follow-up period, 1,280-1,640 days before the anchor (t2) for the 4-year follow-up period, and 1,645-2,005 days before the anchor (t2) for the 5-year follow-up period. Patients were included in a follow-up-specific analysis only when an eligible baseline visit was available. A patient could contribute to more than one follow-up period when the required longitudinal observations were available.
The baseline visit (t0) represented the patient’s clinical state at the beginning of the corresponding follow-up period. MCCs present at baseline defined the patient’s pre-existing MCCs. The pre-existing MCCs were subsequently used to individualize the training population for that patient. MCCs already present at baseline were not considered candidates for newly emerging predictors because they had already occurred. The interval between the baseline (t0) and pre-anchor visit (t1) was used to identify emerging MCCs (a condition absent at baseline (t0) but present by the pre-anchor visit (t1), which we denoted as emerging MCCs in this study. These emerging MCCs represented newly observed conditions that could be evaluated as predictors of dementia status at the subsequent anchor visit.
The anchor (t2), pre-anchor (t1), and baseline visits (t0) served distinct roles. The anchor visit defined the observed dementia outcome. The pre-anchor visit identified the emerging MCCs. The baseline visit defined the patient’s pre-existing MCC profile. Separating the baseline (t0) from the pre-anchor visit (t1) allowed the framework to distinguish pre-existing conditions from conditions emerging during follow-up. Separating the pre-anchor (t1) from the anchor visit (t2) excluded MCCs occurred concurrently with dementia diagnosis.
In potential clinical testing applications, once lazyDT-MCCPath has been developed using the training dataset (Section 2.6), the framework can be applied to a new testing patient at different time points. In general, at the baseline visit (t0), the patient’s pre-existing MCC profile can be used to generate possible individualized MCC pathways and corresponding dementia-risk branches. At a later visit (t1), newly observed MCCs can be entered into the individualized tree to identify the patient’s current pathway and update the predicted dementia risk. After these follow-up MCC values are observed, SHAP can be used as a post hoc local explanation method to identify which emerging MCCs contributed most to the patient-specific dementia-risk prediction (Section 2.8). In this study, we demonstrated a patient example using NACC data in Section 3.4.
2.4. Hold-out Set for Query Patients
For each follow-up period of 3-, 4-, and 5-year, we split the dataset into a training and testing dataset in an 80:20 ratio. Each patient in the test set served as a query patient for whom separate individualized decision tree models were constructed. Training-patient weighting, feature selection, model fitting, and prediction were performed independently for each query patient and follow-up period. We described these steps in detail below.
2.5. Data Processing
We evaluated 16 conditions obtained from clinician-assessed diagnoses in UDS Forms D1 and D2: mild cognitive impairment, cancer, diabetes, myocardial infarction, congestive heart failure, atrial fibrillation, angina, hypercholesterolemia, vitamin B12 deficiency, thyroid disease, arthritis, urinary incontinence, bowel incontinence, sleep apnea, rapid eye movement sleep behavior disorder, and hyposomnia/insomnia. Hypertension was excluded because it was present in all patients at baseline (t0). Each MCC was represented as a binary indicator (0 or 1). A condition was considered present when it was documented in the clinician-assessed forms or when disease-specific medication information indicated its presence by that visit. MCC indicators were updated longitudinally and carried forward after their first documentation. Once a condition was recorded as present, it remained present at subsequent visits.
For each patient and follow-up period, the longitudinal record was represented by three components (discussed in Section 2.3): dementia status at the anchor visit (t2), the eligible MCC states at the pre-anchor visit, t1 (here denoted as predictor MCCs), and the pre-existing MCCs at baseline, t0 (here denoted as pre-existing MCCs).
2.5.1. Dementia Outcome (Label)
The model outcome was binary dementia status (0 or 1) at the anchor visit (t2). Patients were assigned a positive label when dementia was documented and a negative label when they remained free of dementia at their last available NACC visit.
2.5.2. Predictor MCCs
The MCCs absent in the query patient at baseline (t0) formed the eligible predictor set:
For each MCC in P(x*), its binary state at the pre-anchor visit (t1) was used to represent the query patient’s subsequent MCC developments. A value of 1 indicated that the MCC was present at the pre-anchor visit (t1), while a value of 0 indicated that the MCC remained absent. Note that MCCs that were absent at the baseline visit (t0) but present at the pre-anchor visit (t1) were denoted as emerging MCCs in this study.
2.5.3. Pre-Existing MCCs
For query patient (x*), let
denote the set of MCCs present at the baseline visit (t0) among the 16 conditions identified in UDS forms D1 and D2. B(x*) represented the pre-existing MCCs available at the beginning of the patient’s 3-, 4-, or 5-year follow-up period, and it was used to construct the individualized training dataset. B(x*) was not included in the query-specific decision-tree predictor set because it was already present at baseline and could not represent newly emerging MCCs for that patient.
2.6. Model Development
We developed two individualized decision-tree approaches: the proposed lazy decision tree (lazyDT-MCCPath) and an eager decision tree (eagerDT) comparator. Both methods addressed the same research question: given a patient’s pre-existing MCCs, which subsequent MCCs are associated with a higher dementia risk?
To compare, two separate decision trees were constructed for each query patient and each 3-, 4-, or 5-year follow-up period. Decision trees were selected because recursive partitioning can capture nonlinear relationships and interactions among binary MCC indicators while producing interpretable patient-level pathways. At each node, the algorithm selected the MCC and split that produced the greatest reduction in weighted Gini impurity between patients with and without dementia.
lazyDT-MCCPath and eagerDT used the same predictor set, outcome definition, tree architecture, and estimation procedure. Both approaches were implemented using scikit-learn Python (version 3.11.6) package, version 1.8.0 with the Gini impurity criterion, a maximum depth of 5, a cost-complexity pruning parameter of 0.002, and a random seed of 1. To account for the imbalance between patients with and without dementia, class weights were set inversely proportional to the observed class frequencies using the balanced class-weight specification. All remaining parameters were retained at their default values. The two approaches differed only in how the query-specific derivation cohort was constructed. lazyDT-MCCPath applied continuous sample weights based on the number of pre-existing MCCs shared between each derivation patient and the query patient. In contrast, eagerDT used a strict inclusion rule that retained only derivation patients whose pre-existing MCCs contained all MCCs present in the query patient. By holding all other modeling components constant, this comparison isolated the effect of the proposed soft-weighting strategy.
A tree was not fitted when the resulting query-specific derivation cohort contained no eligible patients or included only one dementia outcome class, because a binary classification model could not be estimated. For each successfully fitted tree, the predicted probability of the positive class represented the query patient’s probability of dementia. The binary prediction was generated using the classifier’s default decision rule, and the query patient’s observed pre-anchor MCC states determined the pathway followed from the root node to the terminal prediction.
2.6.1. Proposed Lazy Decision Tree for Dementia Risk Modeling (lazyDT-MCCPath)
lazyDT-MCCPath constructed an individualized decision tree by assigning each training patient a continuous sample weight according to their pre-existing MCC similarity to the query patient (Figure 1). Rather than fitting a regular decision tree (such as eagerDT) that requires complete pre-existing MCCs matching, lazyDT-MCCPath retained the full derivation cohort and progressively increased the influence of patients who shared more pre-existing MCCs with the query patient.
For a training patient j, let B(j) denote the set of MCCs present at that patient’s follow-up-specific baseline visit. The number of pre-existing MCCs shared with the query patient, x* was defined as
The query-specific lazyDT-MCCPath weight for training patient j was then defined as
where γ is a prespecified similarity multiplier.
A training patient with no shared pre-existing MCCs received a weight of 1 because γ0 = 1. The weight increased multiplicatively with each additional shared condition; therefore, patients with greater pre-existing MCC overlap had more influence on impurity reduction and split selection. Patients with partial or no overlap remained in the training cohort but contributed less than patients with more similar pre-existing MCCs.
This soft-weighting strategy was designed to balance personalization with data retention. Assigning equal influence to all training patients could dilute MCC pathways specific to the query patient’s pre-existing MCCs. Conversely, restricting model development to patients with exact or highly specific MCC matches could reduce sample size and, hence, limit generalizability. lazyDT-MCCPath retained the complete training data while emphasizing training patients most similar to the query patient.
We empirically evaluated γ values ranging from 1.5 to 7.0 in increments of 0.5. γ = 3.5 was selected because it achieved the highest AUROC for dementia prediction. After assigning the query-specific weights, lazyDT-MCCPath was fitted using the pre-anchor states of the remaining predictor MCCs, dementia status at the anchor visits as the outcome, and wj(x*)=3.5overlap as the training-patient sample weights.
2.6.2. Eager Decision Tree Comparator (eagerDT)
EagerDT was implemented as a strict cohort-selection comparator to evaluate the contribution of lazyDT-MCCPath’s soft-weighting strategy. Like lazyDT-MCCPath, a separate eagerDT was constructed for each query patient and follow-up period using the same query-specific predictor set, outcome, and tree configuration.
A training patient j was included when their pre-existing MCCs contained every MCC present in the query patient’s pre-existing MCCs:
Training patients satisfying this criterion received a weight of 1. All remaining patients received a weight of 0 and were excluded from model fitting. Thus, a smaller training size is anticipated because of exclusion. On the other hand, training patients could have additional pre-existing MCC information beyond those present in the query patient.
2.7. Model Evaluation
We evaluated lazyDT-MCCPath across the 3-, 4-, and 5-year horizons using two complementary dimensions: individualized model coverage (Section 2.7.1) and predictive performance on the held-out test set (Section 2.7.2).
2.7.1. Model Coverage
We first evaluated whether each method retained sufficient training data to construct individualized models across heterogeneous pre-existing MCCs. For each query patient, training cohort size was defined as the number of patients with a nonzero sample weight. lazyDT-MCCPath retained the complete derivation cohort with continuously varying weights, whereas eagerDT retained only patients satisfying the strict MCC-set inclusion criterion to match the pre-existing conditions.
Because each individualized tree was conditioned on the query patient’s pre-existing MCC pattern, failure to generate a valid tree for a given pattern indicated that the method could not support prediction for patients with that profile. We defined pre-existing MCC pattern coverage as the number and percentage of unique pre-existing MCC patterns for which a valid individualized decision tree was generated. It is used to determine whether each method could generate individualized decision trees across the range of pre-existing MCC profiles observed in held-out query patients. Training cohort size and pre-existing MCC pattern coverage were summarized separately for lazyDT-MCCPath and eagerDT across the 3-, 4-, and 5-year follow-up periods.
2.7.2. Held-out Predictive Performance
Predictive performance was evaluated using patient-level predictions from the held-out test set. To ensure a direct comparison between methods, the analysis was restricted to query patients for whom both lazyDT-MCCPath and eagerDT generated valid predictions. Query patients with only one or two predictor MCCs were also excluded because such a limited feature set was insufficient to characterize complex MCC patterns preceding dementia.
Performance was evaluated separately by model and follow-up period using AUROC. AUROC quantified the ability of each model to rank patients who developed dementia above those who did not across all possible classification thresholds, giving equal consideration to sensitivity and specificity.
2.8. Post Hoc SHAP-Based Interpretation of lazyDT-MCCPath Predictions
We applied TreeSHAP using the SHAP Python package, version 0.46.0, to quantify the contribution of each MCC state to the patient-specific lazyDT-MCCPath prediction. SHAP was used for post hoc prediction interpretation of the query patient after lazyDT-MCCPath generated an individualized decision tree based on the patient’s pre-existing MCC profile. Because pre-existing MCCs were used to personalize the training distribution and excluded from the predictor set, SHAP was applied to the observed pre-anchor values of the remaining eligible MCCs (predictor MCCs). A positive SHAP value indicated that the observed MCC state shifted the prediction toward dementia, whereas a negative SHAP value indicated that it shifted the prediction away from dementia. We defined high-risk emerging MCC signals as conditions that were absent at baseline, present by the pre-anchor visit, and had positive patient-specific SHAP values. These signals were summarized across follow-up periods and pre-existing MCC burden groups, and a patient example was used to illustrate how emerging MCCs contributed to an individualized dementia-risk pathway.
3. Results
3.1. Patient Baseline Characteristics
The 3-, 4-, and 5-year follow-up cohorts included 5,380, 4,505, and 3,138 patients, of whom 8%, 7%, and 5%, respectively, developed dementia by the anchor visit (Table 1). Across these cohorts, the mean age was 74.5 years, 61.7% of patients were female, and 38.3% were male. Most patients were White (82.6%), followed by Black (12.8%), Asian (3.1%), and other racial groups (1.5%).
Patients who developed dementia had a greater pre-existing MCC burden than those who did not. The average number of pre-existing MCCs were 6.5 versus 5.2 during the 3-year follow-up, 6.0 versus 4.9 during the 4-year follow-up, and 5.7 versus 4.8 during the 5-year follow-up. Arthritis (68.0%), hypercholesterolemia (67.5%), and rapid eye movement sleep behavior disorder (63.1%) were the next most prevalent pre-existing MCCs and formed the most common combination of MCC patterns. Congestive heart failure (2.9%), myocardial infarction (4.9%), and bowel incontinence (5.7%) were the least prevalent. Mild cognitive impairment showed the largest difference by dementia outcome and was present at baseline in 60.0% of patients who subsequently developed dementia compared with 18.7% of those who did not.
Patients who developed dementia also accumulated more emerging MCCs during follow-up. The average number of newly developed conditions among patients with and without dementia was 0.6 versus 0.5 at 3 years, 1.0 versus 0.8 at 4 years, and 1.3 versus 1.0 at 5 years. 44% of patients who developed dementia had at least one emerging MCC at 3-year follow-up, and more patients had at least one emerging MCC at 4-year (60%) and 5-year follow-up (69%).
At 3 and 4 years, arthritis, hyposomnia/insomnia, and mild cognitive impairment were among the most frequently observed emerging MCCs in both outcome groups. At 5 years, mild cognitive impairment, hyposomnia/insomnia, and urinary incontinence were most frequent among patients who developed dementia, whereas arthritis, hyposomnia/insomnia, and cancer were more frequent among patients who remained free of dementia.
3.2. Model Coverage and Predictive Performance
lazyDT-MCCPath consistently outperformed eagerDT in both cohort coverage and predictive performance across 3-, 4-, and 5-year follow-ups (Figure 2). Through soft weighting, lazyDT-MCCPath retained the complete derivation cohort for each query patient while assigning greater influence to patients with more similar pre-existing MCCs. In contrast, eagerDT's strict inclusion criterion reduced the average query-specific training cohort to 639 patients at 3 years, 577 at 4 years, and 468 at 5 years. lazyDT-MCCPath therefore retained more than five times as many training patients per query.
The difference in data retention directly affected the range of pre-existing MCC patterns for which an individualized tree could be constructed. lazyDT-MCCPath generated an estimable model for all eligible query patients, whereas eagerDT failed for 17%-33%. Coverage loss under eagerDT was greatest for patients with uncommon or complex pre-existing MCC combinations.
lazyDT-MCCPath also achieved consistently higher predictive performance on the held-out test set. Its AUROC was 0.847 at both the 3- and 4-year follow-ups and 0.813 at the 5-year follow-up, compared with 0.696, 0.609, and 0.692, respectively, for eagerDT. These values corresponded to absolute AUROC improvements of 0.151, 0.238, and 0.121, with the largest improvement observed during the 4-year follow-up.
3.3. Individualized High-risk Emerging MCC Preceding Dementia
Figure 3 summarizes the newly developed MCCs that contributed positively to lazyDT-MCCPath dementia predictions among patients who subsequently developed dementia. Among the 1,071, 891, and 633 held-out query patients at the 3-, 4-, and 5-year follow-up periods, respectively, 80, 66, and 39 developed dementia. Of these patients, 32, 32, and 24 developed at least one emerging MCC. Among patients with at least one emerging MCC, 18 (56%), 21 (66%), and 18 (75%) had at least one SHAP-positive emerging MCC contribution to the dementia prediction at the 3-, 4-, and 5-year follow-up periods, respectively. These patients comprised the final analytic samples for Figure 3. Because individual patients could contribute to more than one high-risk emerging MCC signal, the total frequencies shown in Figure 3 may exceed the number of included patients.
Mild cognitive impairment was the most frequent high-risk emerging MCC across the 3-, 4-, and 5-year follow-up periods, followed by urinary incontinence and arthritis (Figure 3A). Angina and hyposomnia/insomnia were observed less frequently but appeared across multiple follow-up periods. The high-risk emerging MCC also differed according to the number of MCCs already present at baseline (Figure 3B). Among patients with no more than one pre-existing MCC, mild cognitive impairment was the predominant signal. Hyposomnia/insomnia appeared more frequently among patients with 2-3 pre-existing MCCs, whereas urinary incontinence was concentrated among patients with moderate pre-existing burdens of 2-5 MCCs. Arthritis and angina were rarely represented as high-risk signals among patients with low pre-existing burden but appeared more frequently among those with ≥6 pre-existing MCCs. The high-risk MCC pathways further demonstrated variation across specific pre-existing MCCs (Figure 3C). Mild cognitive impairment accounted for the largest proportion of the high-risk emerging MCC pathways at 3 and 5 years, whereas the 4-year pathways were distributed across a wider range of conditions. Excluding mild cognitive impairment and the grouped other-MCC category, patients with arthritis at baseline more frequently had urinary incontinence as a high-risk emerging MCC than angina or hyposomnia/insomnia. A similar pattern was observed among patients with pre-existing thyroid disease. In contrast, among patients with pre-existing hypercholesterolemia, angina, and arthritis occurred more frequently on high-risk pathways than urinary incontinence. Among patients with REM sleep behavior disorder at baseline, arthritis was more frequently represented than angina or urinary incontinence.
3.4. Patient-Specific Dementia Risk Pathway Generated by lazyDT-MCCPath
Figure 4 demonstrates how lazyDT-MCCPath constructs a dementia-risk pathway tailored to an individual patient’s pre-existing MCC patterns. At the beginning of the 5-year follow-up period, the patient had mild cognitive impairment, cancer, myocardial infarction, atrial fibrillation, hypercholesterolemia, urinary incontinence, and rapid eye movement sleep behavior disorder. lazyDT-MCCPath used these pre-existing conditions to define the query-specific weighted training data, while excluding them from the candidate predictors because they were already present. The resulting individualized tree evaluated how the presence or absence of the remaining eligible MCCs could move this patient toward different dementia-risk pathways. Based on the MCC pattern observed during follow-up, lazyDT-MCCPath estimated a dementia probability of 0.820, which was consistent with the patient’s observed outcome at the anchor visit (Figure 4A).
Among the MCCs eligible to emerge after baseline, newly developed angina and arthritis had the largest positive contributions to the patient’s predicted dementia risk, with SHAP values of +0.09 and +0.06, respectively (Figure 4B). Newly developed diabetes had a smaller positive contribution (+0.01), whereas sleep apnea and hyposomnia/insomnia shifted the prediction away from dementia. Because this analysis was retrospective, the patient’s actual emerging MCCs and subsequent dementia outcome were already known. The highlighted decision path therefore represents the observed MCC development followed by this patient and provides patient-level validation that lazyDT-MCCPath assigned a high dementia probability to the observed MCC patterns (Figure 4C).
4. Discussion
This study aimed to identify which emerging MCCs, when combined with specific pre-existing MCCs are associated with progression toward a higher-risk dementia pathway. To address this objective, we developed lazyDT-MCCPath, an individualized modeling framework that combines patient-specific sample weighting with a longitudinal, interpretable decision-tree design. Although sample weighting is an established machine-learning strategy, the contribution of lazyDT-MCCPath lies in its use of pre-existing MCCs to personalize the training distribution while excluding those conditions from the predictor set, thereby focusing the tree on MCCs that remain eligible to emerge during follow-up. This design preserved the transparency of a shallow decision tree while adapting both the training data and the dementia-risk pathways to each patient.
Compared with eagerDT that uses strict cohort selection, lazyDT-MCCPath retained more than five times as many training patients per query and covered all eligible pre-existing MCC patterns. In contrast, eagerDT failed to generate models for 17%-33% of pre-existing MCC patterns. This broader coverage resulted in a consistently stronger predictive performance: lazyDT-MCCPath achieved an average AUROC of 0.83 across all follow-up periods, which was +0.17 higher than eagerDT. Beyond prediction, the individualized pathways showed that the relevance of emerging MCCs depended on the patient’s pre-existing MCC patterns. For example, urinary incontinence appeared more prominently among patients with moderate pre-existing MCC burden, whereas arthritis and angina were more frequently identified among patients with at least six pre-existing MCCs. The patient-level example further illustrated the potential clinical usability of lazyDT-MCCPath by showing potential MCC development preceding dementia that could be monitored before subsequent conditions emerge. lazyDT-MCCPath may therefore complement conventional risk scores by identifying which future MCCs or combinations of conditions could signal movement toward higher dementia risk and warrant closer surveillance or earlier clinical intervention.
A notable finding was that emerging MCCs contributing to higher predicted dementia risk were conditional on both the burden and composition of the patient’s pre-existing MCCs, rather than having uniform relevance across patients (Figure 3). Mild cognitive impairment was the predominant high-risk signal across follow-up periods, consistent with its established association with dementia progression, although progression is neither rapid nor inevitable for most affected individuals[21]. More distinctive were the other noncognitive pathways. Hyposomnia/insomnia appeared more frequently as a high-dementia-risk signal among patients with 2-3 pre-existing MCCs. This aligns with emerging evidence that poor sleep may partly mediate the relationship between multimorbidity and cognitive decline and that abnormal sleep duration is associated with poorer cognition among patients with multimorbidity [22]. Angina was more frequently identified among patients with greater MCC burden, particularly those with pre-existing hypercholesterolemia. This is consistent with a cumulative vascular pathway in which hypercholesterolemia increases coronary disease risk, incident coronary events are followed by accelerated cognitive decline, and dementia risk rises when coronary disease co-occurs with other cardiometabolic conditions [11,23]. Urinary incontinence, by contrast, was more prominent among patients with moderate MCC burden and pre-existing arthritis, whereas arthritis appeared more often among patients with at least six pre-existing MCCs and in pathways beginning with REM sleep behavior disorder. Although urinary incontinence, osteoarthritis, thyroid disease, and rapid eye movement sleep behavior disorder have each been associated with cognitive impairment or dementia [24,25,26,27], the specific MCC-dependent risk signals identified by lazyDT-MCCPath have not been established previously and should be interpreted as hypothesis-generating indicators of neurologic, functional, inflammatory, vascular, or broader multisystem vulnerability. Because these pathway analyses were based on the relatively small subset of patients who both developed an emerging MCC and subsequently developed dementia, the observed patterns should not be interpreted as stable population-level associations. Nevertheless, they demonstrate the potential of lazyDT-MCCPath to move beyond average risk-factor effects and identify which emerging condition may become informative for an individual patient’s dementia-risk pathways.
In the illustrative patient example (Figure 4), newly developed angina and arthritis were the strongest positive contributors to the dementia prediction, and the observed MCC patterns ended in a terminal node with an estimated dementia probability of 82%. Because the patient’s subsequent MCCs and outcome were known retrospectively, this example provides evidence that the lazyDT-MCCPath captured clinically relevant changes preceding dementia. The same tree also contained alternative branches that the patient did not follow, each representing a different combination of future MCC states and an associated dementia probability. These branches are learned from observations of similar patients in the training data. In real-world applications, these higher-risk branches could be used to identify which conditions or combinations warrant closer surveillance before the eventual dementia-risk pathway is known. For example, monitoring could be prioritized toward vascular, urinary, sleep, mobility, or functional changes according to the patient’s specific pre-existing MCCs rather than applying the same surveillance strategy to all patients. lazyDT-MCCPath may support prevention-oriented surveillance by identifying patient-specific emerging MCCs associated with higher predicted dementia risk. However, whether managing those conditions changes dementia incidence requires prospective interventional evaluation.
This study had several limitations. The NACC cohort consists largely of research volunteers evaluated at Alzheimer’s Disease Research Centers and may not represent patients receiving routine community care. Dementia occurred in only 5%-8% of the follow-up cohorts, and the number of patients who both developed dementia and experienced a new MCC was smaller. As a result, the sample size for high-risk MCC signals was small, so the frequencies should be interpreted as exploratory rather than as stable population-level estimates. However, these patterns remain valuable as proof-of-concept evidence that lazyDT-MCCPath can extract clinically interpretable, patient-specific risk signals from sparse longitudinal events. In addition, the current model represented 16 MCCs as binary indicators and did not incorporate disease severity, treatment, biomarkers, social determinants, or functional measures. Accordingly, the study results reflect predictive associations between MCC patterns and dementia risk rather than causal relationships or intervention effects. Because all eligible MCC states were measured at the pre-anchor visit, the order of splits within a tree should be interpreted as a predictive decision path rather than the chronological order of MCC development. Finally, the comparative performance analysis was restricted to patients for whom both lazyDT-MCCPath and eagerDT generated valid predictions.
Future studies should externally validate lazyDT-MCCPath in larger and more representative longitudinal cohorts. Incorporating additional clinical information, such as disease severity, treatment, and syndemic factors, may further refine the pathways. Prospective studies will be particularly important for determining whether monitoring or managing modifiable conditions identified on higher-risk branches improves cognitive outcomes.
Author Contributions
Conceptualization, C.L.C., T.J.A, B.S., T.M., P.J.T., N.C.C., Y.C.C., J.S., and R.Z.; methodology, C.L.C., F.X. and P.Y.Y.; validation, W.Z. and R.A.E.K.; formal analysis, P.Y.Y.; data curation, P.Y.Y. and R.A.E.K.; writing—original draft preparation, C.L.C. and P.Y.Y.; writing—review and editing, P.J.T, B.S., T.M., F.X., and T.J.A.; visualization, P.Y.Y.; supervision, C.L.C.; All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
This study was reviewed by the Institutional Review Board (or Ethics Committee) of the University of Minnesota and determined non-human research (IRB number = STUDY00018672).
Informed Consent Statement
Informed consent was obtained from all NACC participants and co-participants.
Data Availability Statement
The data analyzed in this study were obtained from the NACC and are available to qualified researchers through the NACC data request process, subject to NACC approval, data use policies, and applicable data use requirements. The authors do not have permission to redistribute NACC data.
Acknowledgments
The NACC database is funded by NIA/NIH Grant U24 AG072122. NACC data are contributed by the NIA-funded ADRCs: P30 AG062429 (PI James Brewer, MD, PhD), P30 AG066468 (PI Oscar Lopez, MD), P30 AG062421 (PI Bradley Hyman, MD, PhD), P30 AG066509 (PI Thomas Grabowski, MD), P30 AG066514 (PI Mary Sano, PhD), P30 AG066530 (PI Helena Chui, MD), P30 AG066507 (PI Marilyn Albert, PhD), P30 AG066444 (PI John Morris, MD), P30 AG066518 (PI Jeffrey Kaye, MD), P30 AG066512 (PI Thomas Wisniewski, MD), P30 AG066462 (PI Scott Small, MD), P30 AG072979 (PI David Wolk, MD), P30 AG072972 (PI Charles DeCarli, MD), P30 AG072976 (PI Andrew Saykin, PsyD), P30 AG072975 (PI David Bennett, MD), P30 AG072978 (PI Neil Kowall, MD), P30 AG072977 (PI Robert Vassar, PhD), P30 AG066519 (PI Frank LaFerla, PhD), P30 AG062677 (PI Ronald Petersen, MD, PhD), P30 AG079280 (PI Eric Reiman, MD), P30 AG062422 (PI Gil Rabinovici, MD), P30 AG066511 (PI Allan Levey, MD, PhD), P30 AG072946 (PI Linda Van Eldik, PhD), P30 AG062715 (PI Sanjay Asthana, MD, FRCP), P30 AG072973 (PI Russell Swerdlow, MD), P30 AG066506 (PI Todd Golde, MD, PhD), P30 AG066508 (PI Stephen Strittmatter, MD, PhD), P30 AG066515 (PI Victor Henderson, MD, MS), P30 AG072947 (PI Suzanne Craft, PhD), P30 AG072931 (PI Henry Paulson, MD, PhD), P30 AG066546 (PI Sudha Seshadri, MD), P20 AG068024 (PI Erik Roberson, MD, PhD), P20 AG068053 (PI Justin Miller, PhD), P20 AG068077 (PI Gary Rosenberg, MD), P20 AG068082 (PI Angela Jefferson, PhD), P30 AG072958 (PI Heather Whitson, MD), P30 AG072959 (PI James Leverenz, MD). During the preparation of this manuscript/study, the author(s) used [tool name, version information] for the purposes of [description of use]. The authors have reviewed and edited the output and take full responsibility for the content of this publication.”.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| NACC | National Alzheimer’s Coordinating Center |
| eagerDT | Eager Decision Tree |
| ADRD | Alzheimer’s Disease and Related Dementia |
| MCC | Multiple Chronic Condition |
| AUROC | Area Under the Receiver Operating Characteristic Curve |
| AI/ML | Artificial Intelligence/Machine Learning |
References
- 2025 Alzheimer’s Disease Facts and Figures. Alzheimers Dement 2025, 21, e70235. [CrossRef]
- Barnett, K.; Mercer, S.W.; Norbury, M.; Watt, G.; Wyke, S.; Guthrie, B. Epidemiology of Multimorbidity and Implications for Health Care, Research, and Medical Education: A Cross-Sectional Study. Lancet 2012, 380, 37–43. [Google Scholar] [CrossRef] [PubMed]
- Beerten, S.G.; Helsen, A.; De Lepeleire, J.; Waldorff, F.B.; Vaes, B. Trends in Prevalence and Incidence of Registered Dementia and Trends in Multimorbidity among Patients with Dementia in General Practice in Flanders, Belgium, 2000-2021: A Registry-Based, Retrospective, Longitudinal Cohort Study. BMJ Open 2022, 12, e063891. [Google Scholar] [CrossRef] [PubMed]
- Hu, H.-Y.; Zhang, Y.-R.; Aerqin, Q.; Ou, Y.-N.; Wang, Z.-T.; Cheng, W.; Feng, J.-F.; Tan, L.; Yu, J.-T. Association between Multimorbidity Status and Incident Dementia: A Prospective Cohort Study of 245,483 Participants. Transl. Psychiatry 2022, 12. [Google Scholar] [CrossRef] [PubMed]
- Calvin, C.M.; Conroy, M.C.; Moore, S.F.; Kuźma, E.; Littlejohns, T.J. Association of Multimorbidity, Disease Clusters, and Modification by Genetic Factors With Risk of Dementia. JAMA Netw. Open 2022, 5, e2232124. [Google Scholar] [CrossRef] [PubMed]
- Veronese, N.; Koyanagi, A.; Dominguez, L.J.; Maggi, S.; Soysal, P.; Bolzetta, F.; Vernuccio, L.; Smith, L.; Matranga, D.; Barbagallo, M. Multimorbidity Increases the Risk of Dementia: A 15 Year Follow-up of the SHARE Study. Age Ageing 2023, 52, afad052. [Google Scholar] [CrossRef] [PubMed]
- Chowdhury, S.R.; Das, D.C.; Sunna, T.C.; Beyene, J.; Hossain, A. Global and Regional Prevalence of Multimorbidity in the Adult Population in Community Settings: A Systematic Review and Meta-Analysis. eClinicalMedicine 2023, 57. [Google Scholar] [CrossRef] [PubMed]
- Chatterjee, S.; Mudher, A. Alzheimer’s Disease and Type 2 Diabetes: A Critical Assessment of the Shared Pathological Traits. Front Neurosci. 2018, 12, 383. [Google Scholar] [CrossRef] [PubMed]
- Ownby, R.L.; Crocco, E.; Acevedo, A.; John, V.; Loewenstein, D. Depression and Risk for Alzheimer Disease: Systematic Review, Meta-Analysis, and Metaregression Analysis. Arch. Gen. Psychiatry 2006, 63, 530–538. [Google Scholar] [CrossRef] [PubMed]
- Diniz, B.S.; Teixeira, A.L.; Cao, F.; Gildengers, A.; Soares, J.C.; Butters, M.A.; Reynolds, Charles F., III. History of Bipolar Disorder and the Risk of Dementia: A Systematic Review and Meta-Analysis. The American journal of geriatric psychiatry : official journal of the American Association for Geriatric Psychiatry 2017, 25, 357. [Google Scholar] [CrossRef] [PubMed]
- Tai, X.Y.; Veldsman, M.; Lyall, D.M.; Littlejohns, T.J.; Langa, K.M.; Husain, M.; Ranson, J.; Llewellyn, D.J. Cardiometabolic Multimorbidity, Genetic Risk, and Dementia: A Prospective Cohort Study. Lancet Healthy Longev. 2022, 3, e428–e436. [Google Scholar] [CrossRef] [PubMed]
- Grande, G.; Marengoni, A.; Vetrano, D.L.; Roso-Llorach, A.; Rizzuto, D.; Zucchelli, A.; Qiu, C.; Fratiglioni, L.; Calderón-Larrañaga, A. Multimorbidity Burden and Dementia Risk in Older Adults: The Role of Inflammation and Genetics. Alzheimers Dement 2021, 17, 768–776. [Google Scholar] [CrossRef] [PubMed]
- Calderón-Larrañaga, A.; Vetrano, D.L.; Ferrucci, L.; Mercer, S.W.; Marengoni, A.; Onder, G.; Eriksdotter, M.; Fratiglioni, L. Multimorbidity and Functional Impairment–Bidirectional Interplay, Synergistic Effects and Common Pathways. J. Intern. Med. 2019, 285, 255–271. [Google Scholar] [CrossRef] [PubMed]
- Dove, A.; Marseglia, A.; Shang, Y.; Grande, G.; Vetrano, D.L.; Laukka, E.J.; Fratiglioni, L.; Xu, W. Cardiometabolic Multimorbidity Accelerates Cognitive Decline and Dementia Progression. Alzheimer’s Dement. 2023, 19, 821–830. [Google Scholar] [CrossRef] [PubMed]
- Prados-Torres, A.; Calderón-Larrañaga, A.; Hancco-Saavedra, J.; Poblador-Plou, B.; Akker, M. van den Multimorbidity Patterns: A Systematic Review. J. Clin. Epidemiol. 2014, 67, 254–266. [Google Scholar] [CrossRef] [PubMed]
- Ferris, J.K.; Fiedeldey, L.K.; Kim, B.; Clemens, F.; Irvine, M.A.; Hosseini, S.H.; Smolina, K.; Wister, A. A Systematic Review and Meta-Analysis of Disease Clusters in Multimorbidity. Nat. Commun. 2025, 17, 634. [Google Scholar] [CrossRef] [PubMed]
- Schäfer, I.; von Leitner, E.-C.; Schön, G.; Koller, D.; Hansen, H.; Kolonko, T.; Kaduszkiewicz, H.; Wegscheider, K.; Glaeske, G.; Bussche, H. van den Multimorbidity Patterns in the Elderly: A New Approach of Disease Clustering Identifies Complex Interrelations between Chronic Conditions. PLoS ONE 2010, 5, e15941. [Google Scholar] [CrossRef] [PubMed]
- Vetrano, D.L.; Roso-Llorach, A.; Fernández, S.; Guisado-Clavero, M.; Violán, C.; Onder, G.; Fratiglioni, L.; Calderón-Larrañaga, A.; Marengoni, A. Twelve-Year Clinical Trajectories of Multimorbidity in a Population of Older Adults. Nat. Commun. 2020, 11, 3223. [Google Scholar] [CrossRef] [PubMed]
- Yew, P.Y.; Devera, R.; Liang, Y.; Khalifa, R.A.E.; Sun, J.; Chi, N.-C.; Chou, Y.-C.; Tonellato, P.J.; Chi, C.-L. Unraveling the Multiple Chronic Conditions Patterns among People with Alzheimer’s Disease and Related Dementia: A Machine Learning Approach to Incorporate Synergistic Interactions. Alzheimers Dement 2024, 20, 4818–4827. [Google Scholar] [CrossRef] [PubMed]
- Beekly, D.L.; Ramos, E.M.; Lee, W.W.; Deitrich, W.D.; Jacka, M.E.; Wu, J.; Hubbard, J.L.; Koepsell, T.D.; Morris, J.C.; Kukull, W.A.; et al. The National Alzheimer’s Coordinating Center (NACC) Database: The Uniform Data Set. Alzheimer Dis. Assoc. Disord. 2007, 21, 249–258. [Google Scholar] [CrossRef] [PubMed]
- Mitchell, A.J.; Shiri-Feshki, M. Rate of Progression of Mild Cognitive Impairment to Dementia--Meta-Analysis of 41 Robust Inception Cohort Studies. Acta Psychiatr. Scand. 2009, 119, 252–265. [Google Scholar] [CrossRef] [PubMed]
- Wang, M.; Huang, S.; Zhang, X.; Fu, J.; Zhang, Y.; Wang, X.; Zhou, H. Multimorbidity and Cognitive Function in Community-Dwelling Older Adults in Shanghai: The Mediating Role of Sleep Quality. J. Sleep Res. 2026, e70297. [Google Scholar] [CrossRef] [PubMed]
- Xie, W.; Zheng, F.; Yan, L.; Zhong, B. Cognitive Decline Before and After Incident Coronary Events. J. Am. Coll. Cardiol. 2019, 73, 3041–3050. [Google Scholar] [CrossRef] [PubMed]
- Bartolone, S.N.; Sharma, P.; Chancellor, M.B.; Lamb, L.E. Urinary Incontinence and Alzheimer’s Disease: Insights From Patients and Preclinical Models. Front Aging Neurosci. 2021, 13, 777819. [Google Scholar] [CrossRef] [PubMed]
- Weber, A.; Mak, S.H.; Berenbaum, F.; Sellam, J.; Zheng, Y.-P.; Han, Y.; Wen, C. Association between Osteoarthritis and Increased Risk of Dementia: A Systemic Review and Meta-Analysis. Medicine 2019, 98, e14355. [Google Scholar] [CrossRef] [PubMed]
- Wieland, D.R.; Wieland, J.R.; Wang, H.; Chen, Y.-H.; Lin, C.-H.; Wang, J.-J.; Weng, C.-H. Thyroid Disorders and Dementia Risk: A Nationwide Population-Based Case-Control Study. Neurology 2022, 99, e679–e687. [Google Scholar] [CrossRef] [PubMed]
- Postuma, R.B.; Iranzo, A.; Hu, M.; Högl, B.; Boeve, B.F.; Manni, R.; Oertel, W.H.; Arnulf, I.; Ferini-Strambi, L.; Puligheddu, M.; et al. Risk and Predictors of Dementia and Parkinsonism in Idiopathic REM Sleep Behaviour Disorder: A Multicentre Study. Brain 2019, 142, 744–759. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
lazyDT-MCCPath framework for dementia-risk modeling. The figure above shows 8 steps to visualize an individual’s MCC paths and potential emerging MCCs. The baseline visit defined the patient’s pre-existing MCC profile, the pre-anchor visit captured MCC states immediately before outcome assessment, and the anchor visit defined dementia status. Each held-out test patient served as a query patient. MCCs present at baseline were used to personalize the training data, whereas MCCs absent at baseline formed the eligible predictor set. Each training patient received a query-specific sample weight, and the resulting lazyDT-MCCPath uses the eligible predictor set at the pre-anchor visit to estimate dementia probability and display potential MCC pathways conditional on the query patient’s baseline profile.
Figure 1.
lazyDT-MCCPath framework for dementia-risk modeling. The figure above shows 8 steps to visualize an individual’s MCC paths and potential emerging MCCs. The baseline visit defined the patient’s pre-existing MCC profile, the pre-anchor visit captured MCC states immediately before outcome assessment, and the anchor visit defined dementia status. Each held-out test patient served as a query patient. MCCs present at baseline were used to personalize the training data, whereas MCCs absent at baseline formed the eligible predictor set. Each training patient received a query-specific sample weight, and the resulting lazyDT-MCCPath uses the eligible predictor set at the pre-anchor visit to estimate dementia probability and display potential MCC pathways conditional on the query patient’s baseline profile.
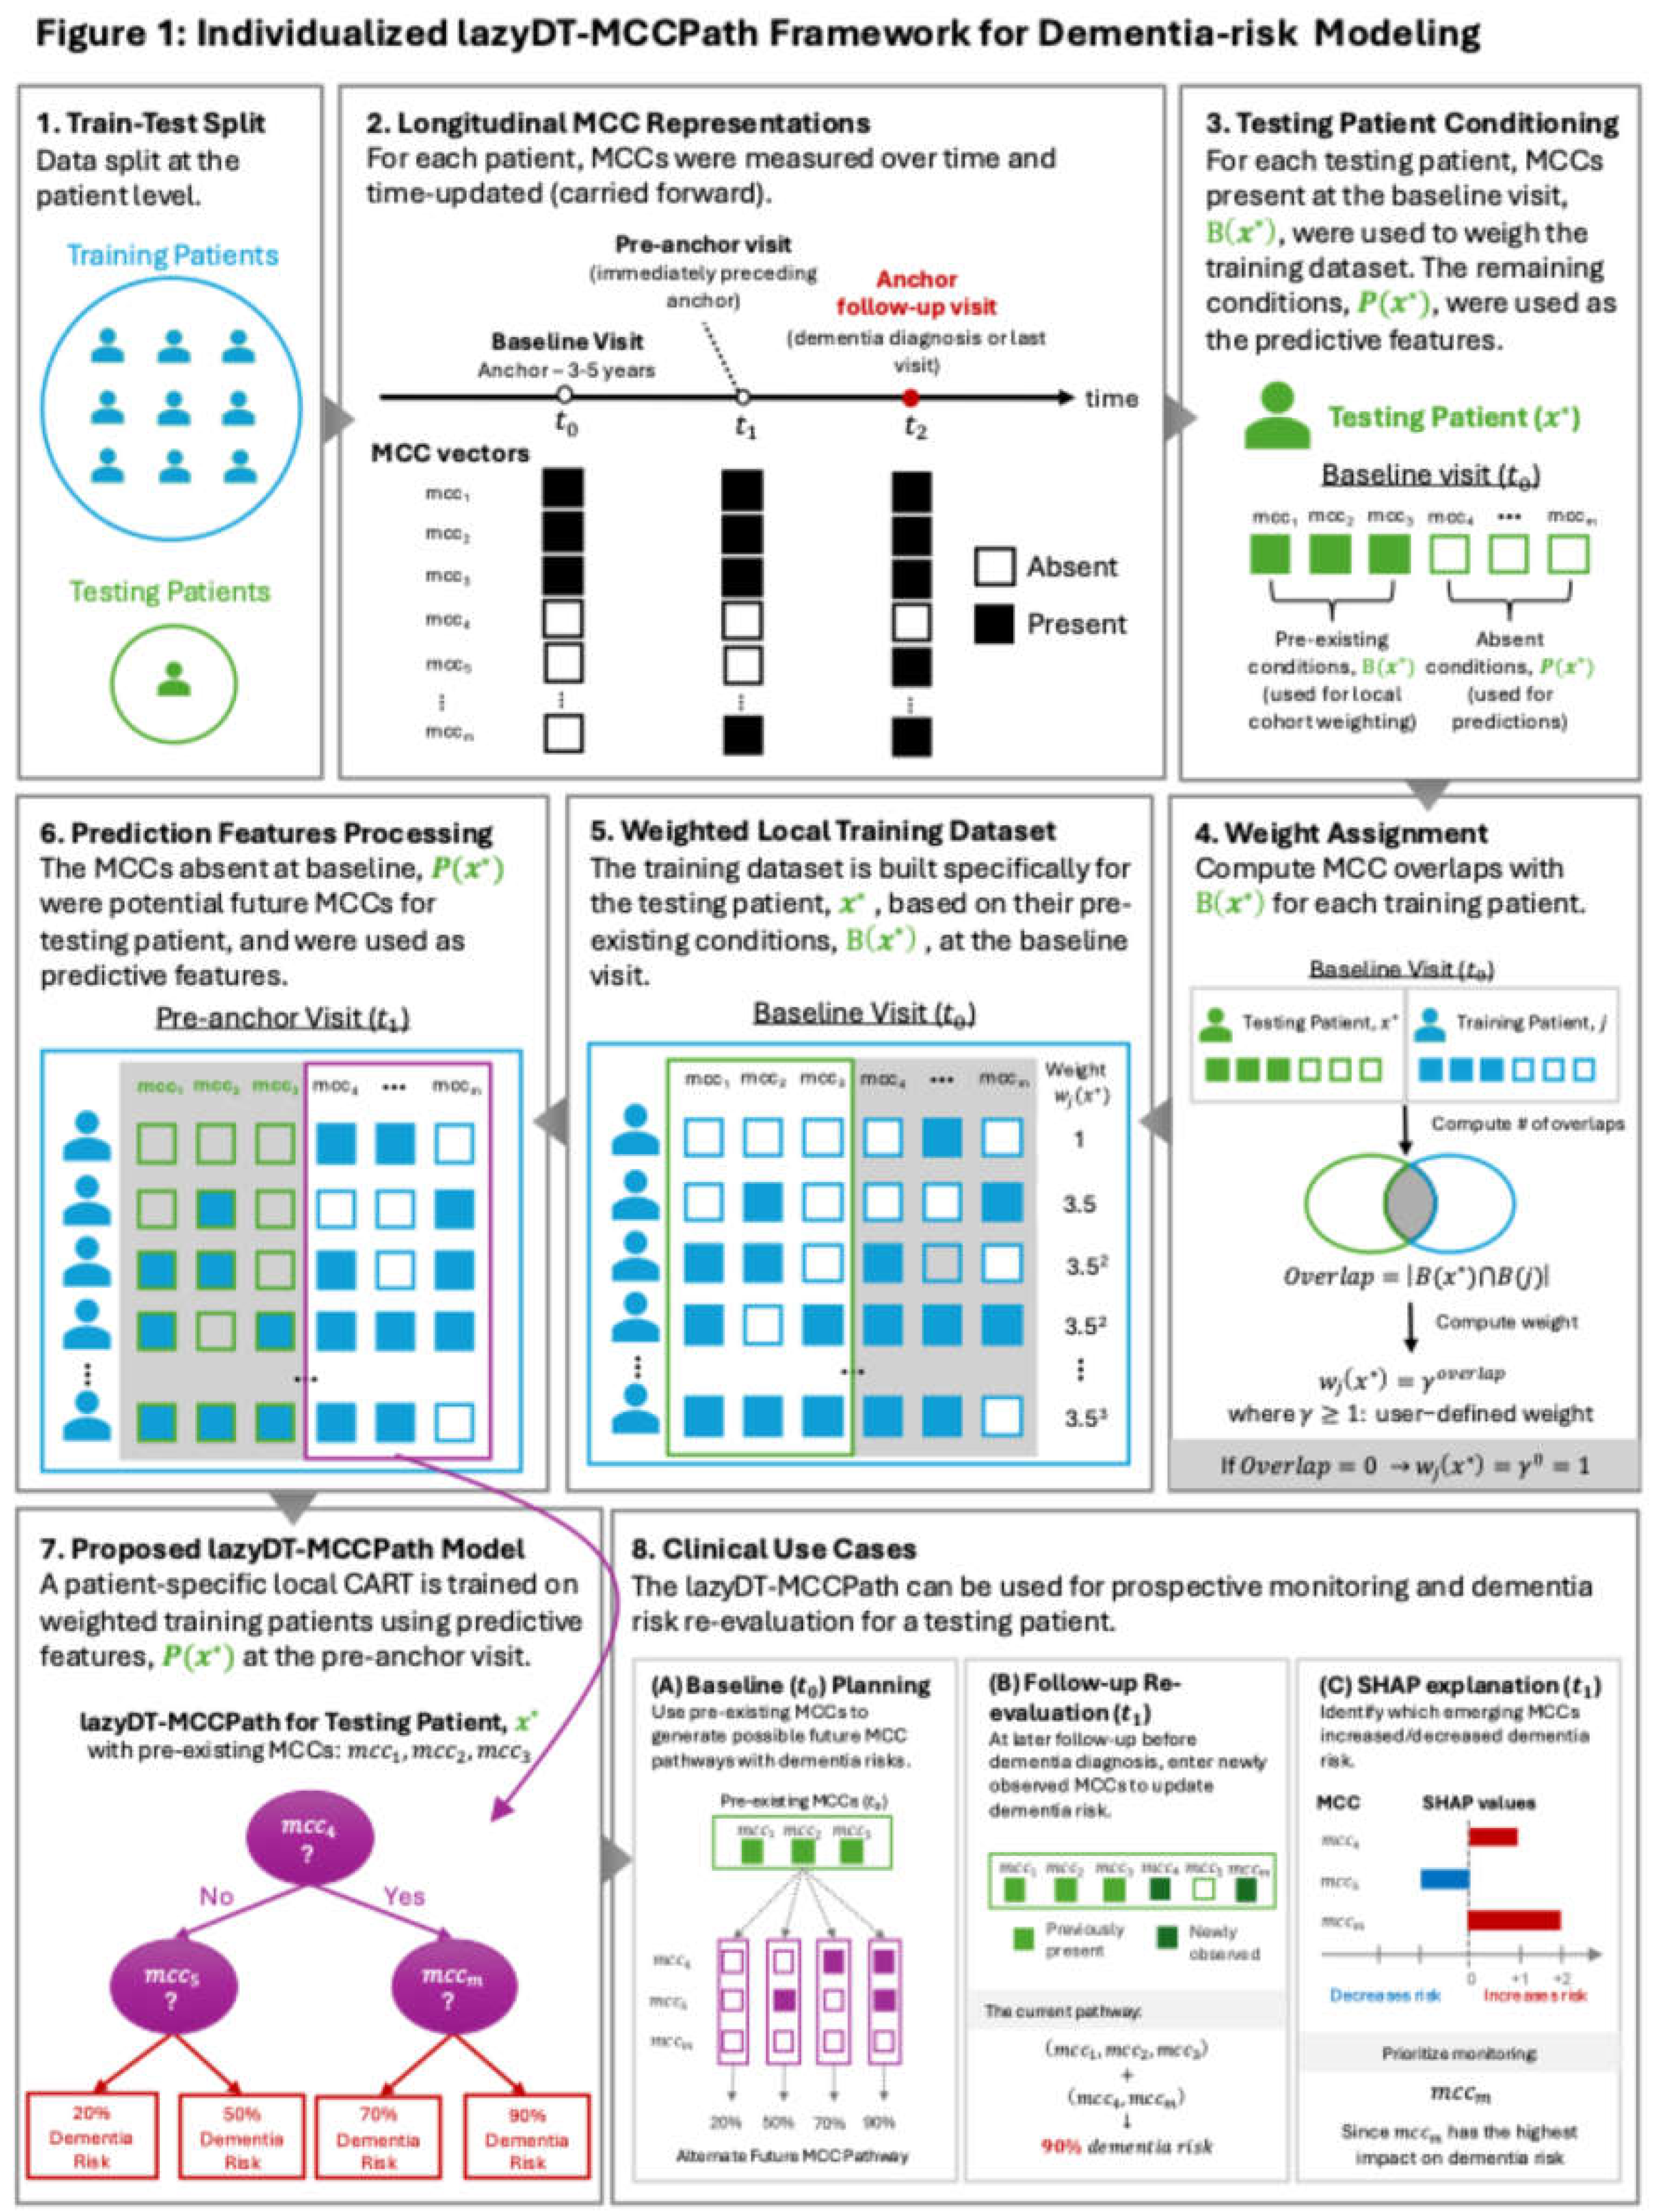
Figure 2.
Cohort coverage and predictive performance of individualized decision trees. Comparison of eagerDT, which uses strict pre-existing MCC inclusion, and lazyDT-MCCPath, which applies soft weighting based on similarity to each query patient’s pre-existing MCCs, across 3-, 4-, and 5-year follow-ups. Panels show (A) the average training cohort size, (B) the number of unique pre-existing MCC patterns, and (C) the average AUROC.
Figure 2.
Cohort coverage and predictive performance of individualized decision trees. Comparison of eagerDT, which uses strict pre-existing MCC inclusion, and lazyDT-MCCPath, which applies soft weighting based on similarity to each query patient’s pre-existing MCCs, across 3-, 4-, and 5-year follow-ups. Panels show (A) the average training cohort size, (B) the number of unique pre-existing MCC patterns, and (C) the average AUROC.
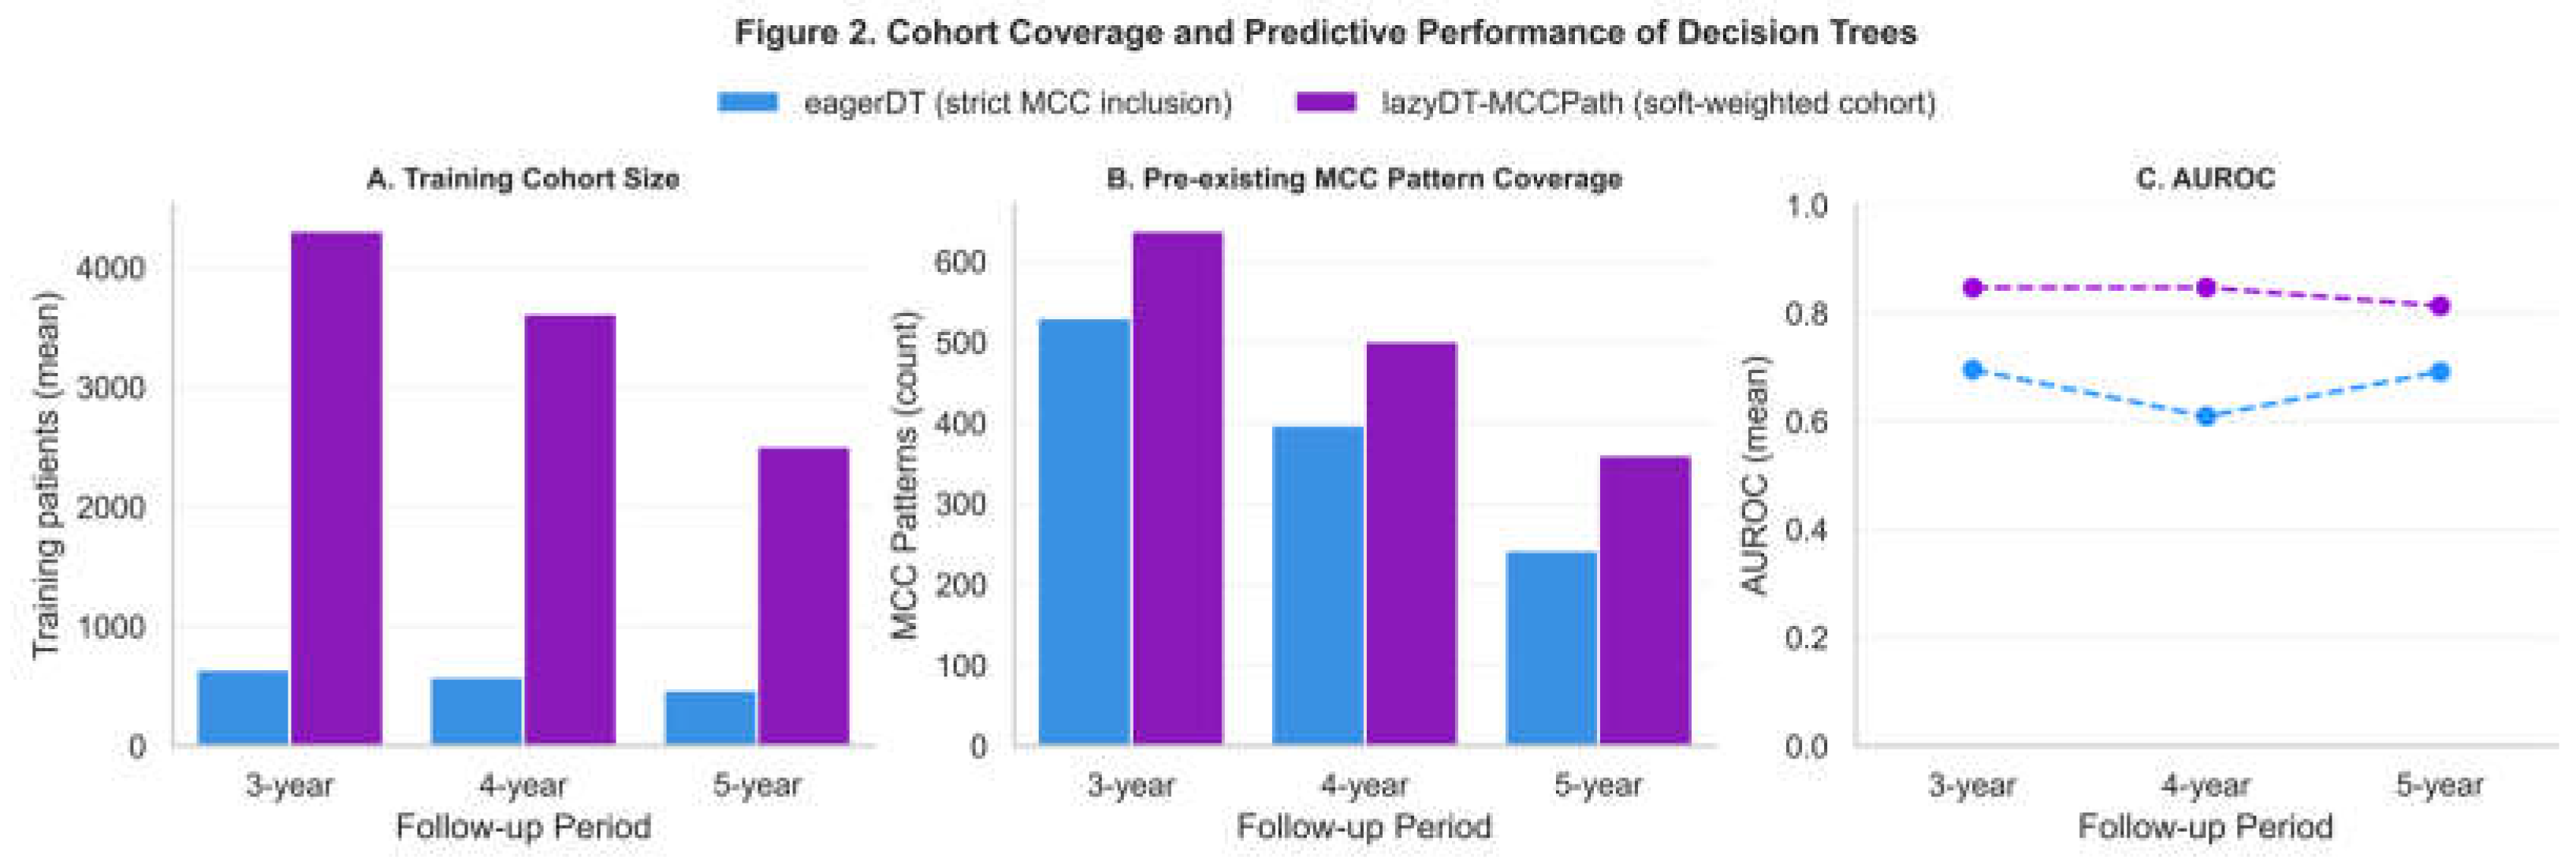
Figure 3.
Individualized High-risk Emerging Multiple Chronic Conditions (MCCs) Preceding Dementia. This figure shows the emerging MCCs associated with higher predicted dementia risk (positive SHAP values) among patients who subsequently developed dementia. Panel A shows the number of patients for whom each emerging MCC had positive SHAP values under lazyDT-MCCPath across the 3-, 4-, and 5-year follow-ups. Panel B shows the frequency of these high-dementia-risk MCCs according to pre-existing MCC burden. Panel C illustrates individualized MCC pathways linking selected pre-existing MCCs to high-risk emerging MCCs and observed dementia development. Path width represents the number of patients following each pathway and should be interpreted as frequency rather than the magnitude of risk.
Figure 3.
Individualized High-risk Emerging Multiple Chronic Conditions (MCCs) Preceding Dementia. This figure shows the emerging MCCs associated with higher predicted dementia risk (positive SHAP values) among patients who subsequently developed dementia. Panel A shows the number of patients for whom each emerging MCC had positive SHAP values under lazyDT-MCCPath across the 3-, 4-, and 5-year follow-ups. Panel B shows the frequency of these high-dementia-risk MCCs according to pre-existing MCC burden. Panel C illustrates individualized MCC pathways linking selected pre-existing MCCs to high-risk emerging MCCs and observed dementia development. Path width represents the number of patients following each pathway and should be interpreted as frequency rather than the magnitude of risk.
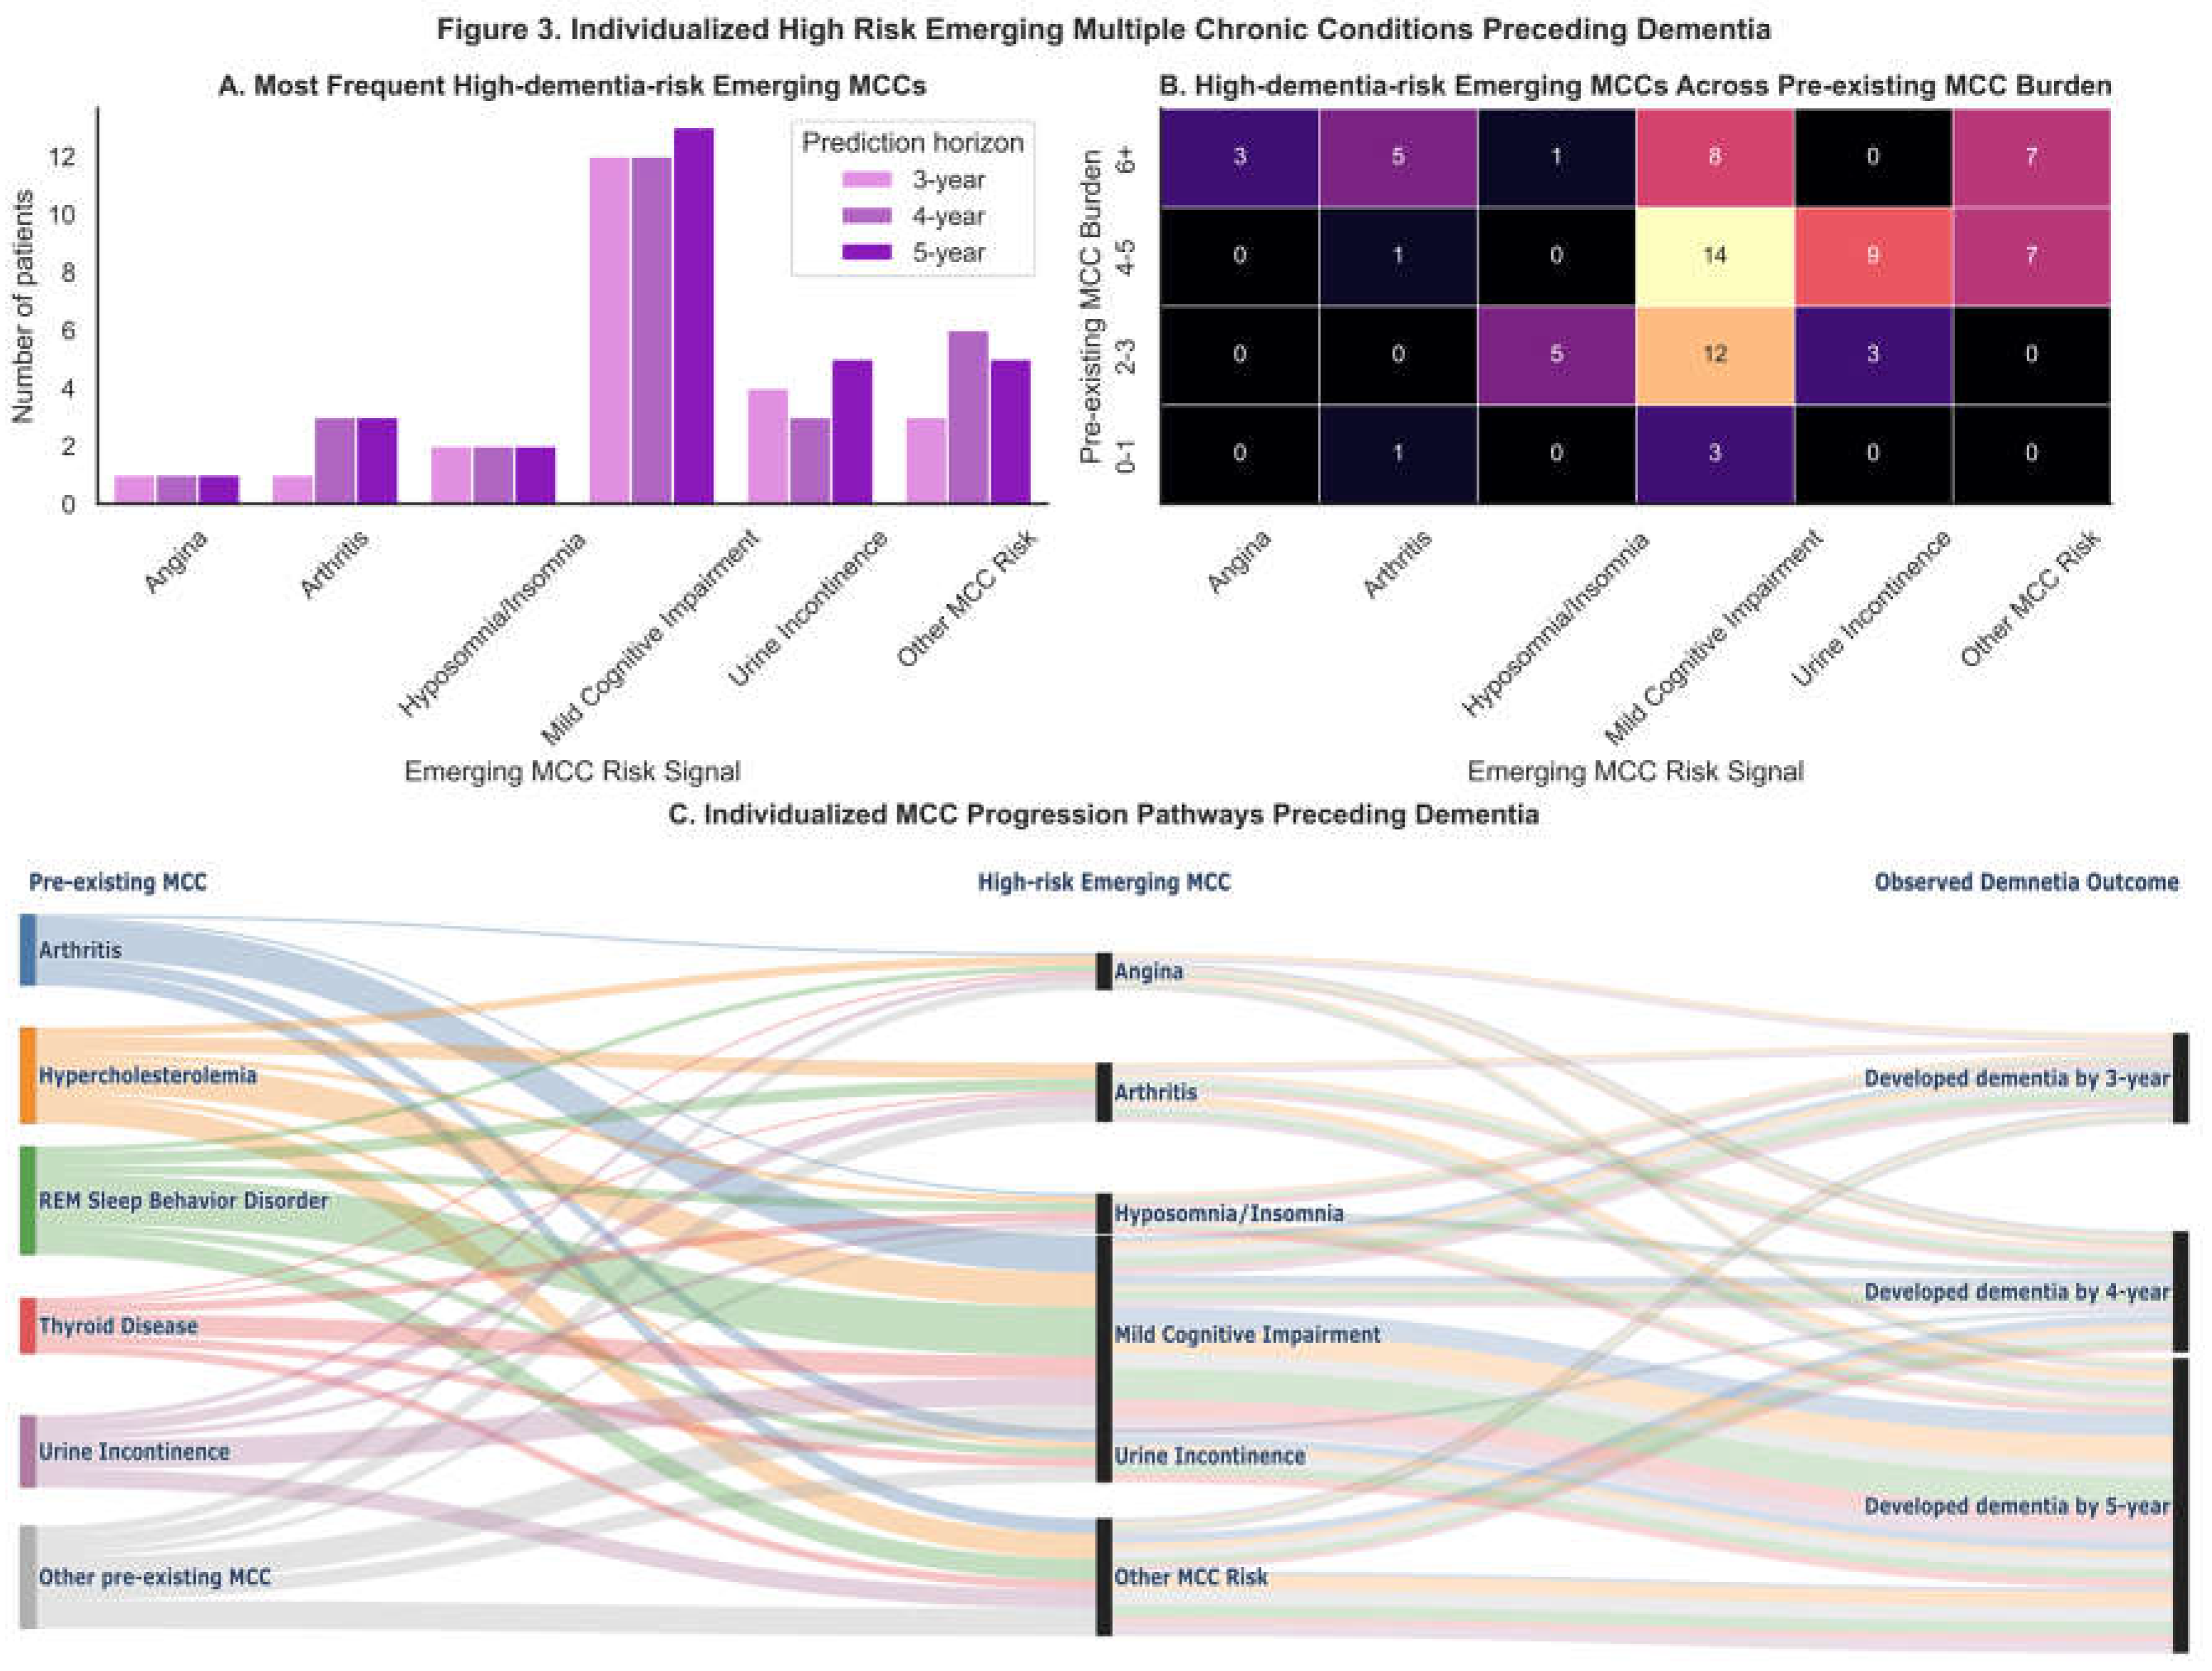
Figure 4.
Patient-specific lazyDT-MCCPath Explanation of Dementia Risk. Example of an individualized 5-year dementia prediction generated by lazyDT-MCCPath. Panel A summarizes the patient’s pre-existing MCCs, newly developed emerging MCCs, predicted dementia probability, and observed outcome. Panel B shows the SHAP contribution of each eligible emerging MCC state to the patient’s predicted dementia risk. Panel C presents the individualized lazyDT-MCCPath and highlights the patient’s observed decision pathway in purple. Non-path branches represent alternative MCC combinations within the patient-specific tree.
Figure 4.
Patient-specific lazyDT-MCCPath Explanation of Dementia Risk. Example of an individualized 5-year dementia prediction generated by lazyDT-MCCPath. Panel A summarizes the patient’s pre-existing MCCs, newly developed emerging MCCs, predicted dementia probability, and observed outcome. Panel B shows the SHAP contribution of each eligible emerging MCC state to the patient’s predicted dementia risk. Panel C presents the individualized lazyDT-MCCPath and highlights the patient’s observed decision pathway in purple. Non-path branches represent alternative MCC combinations within the patient-specific tree.
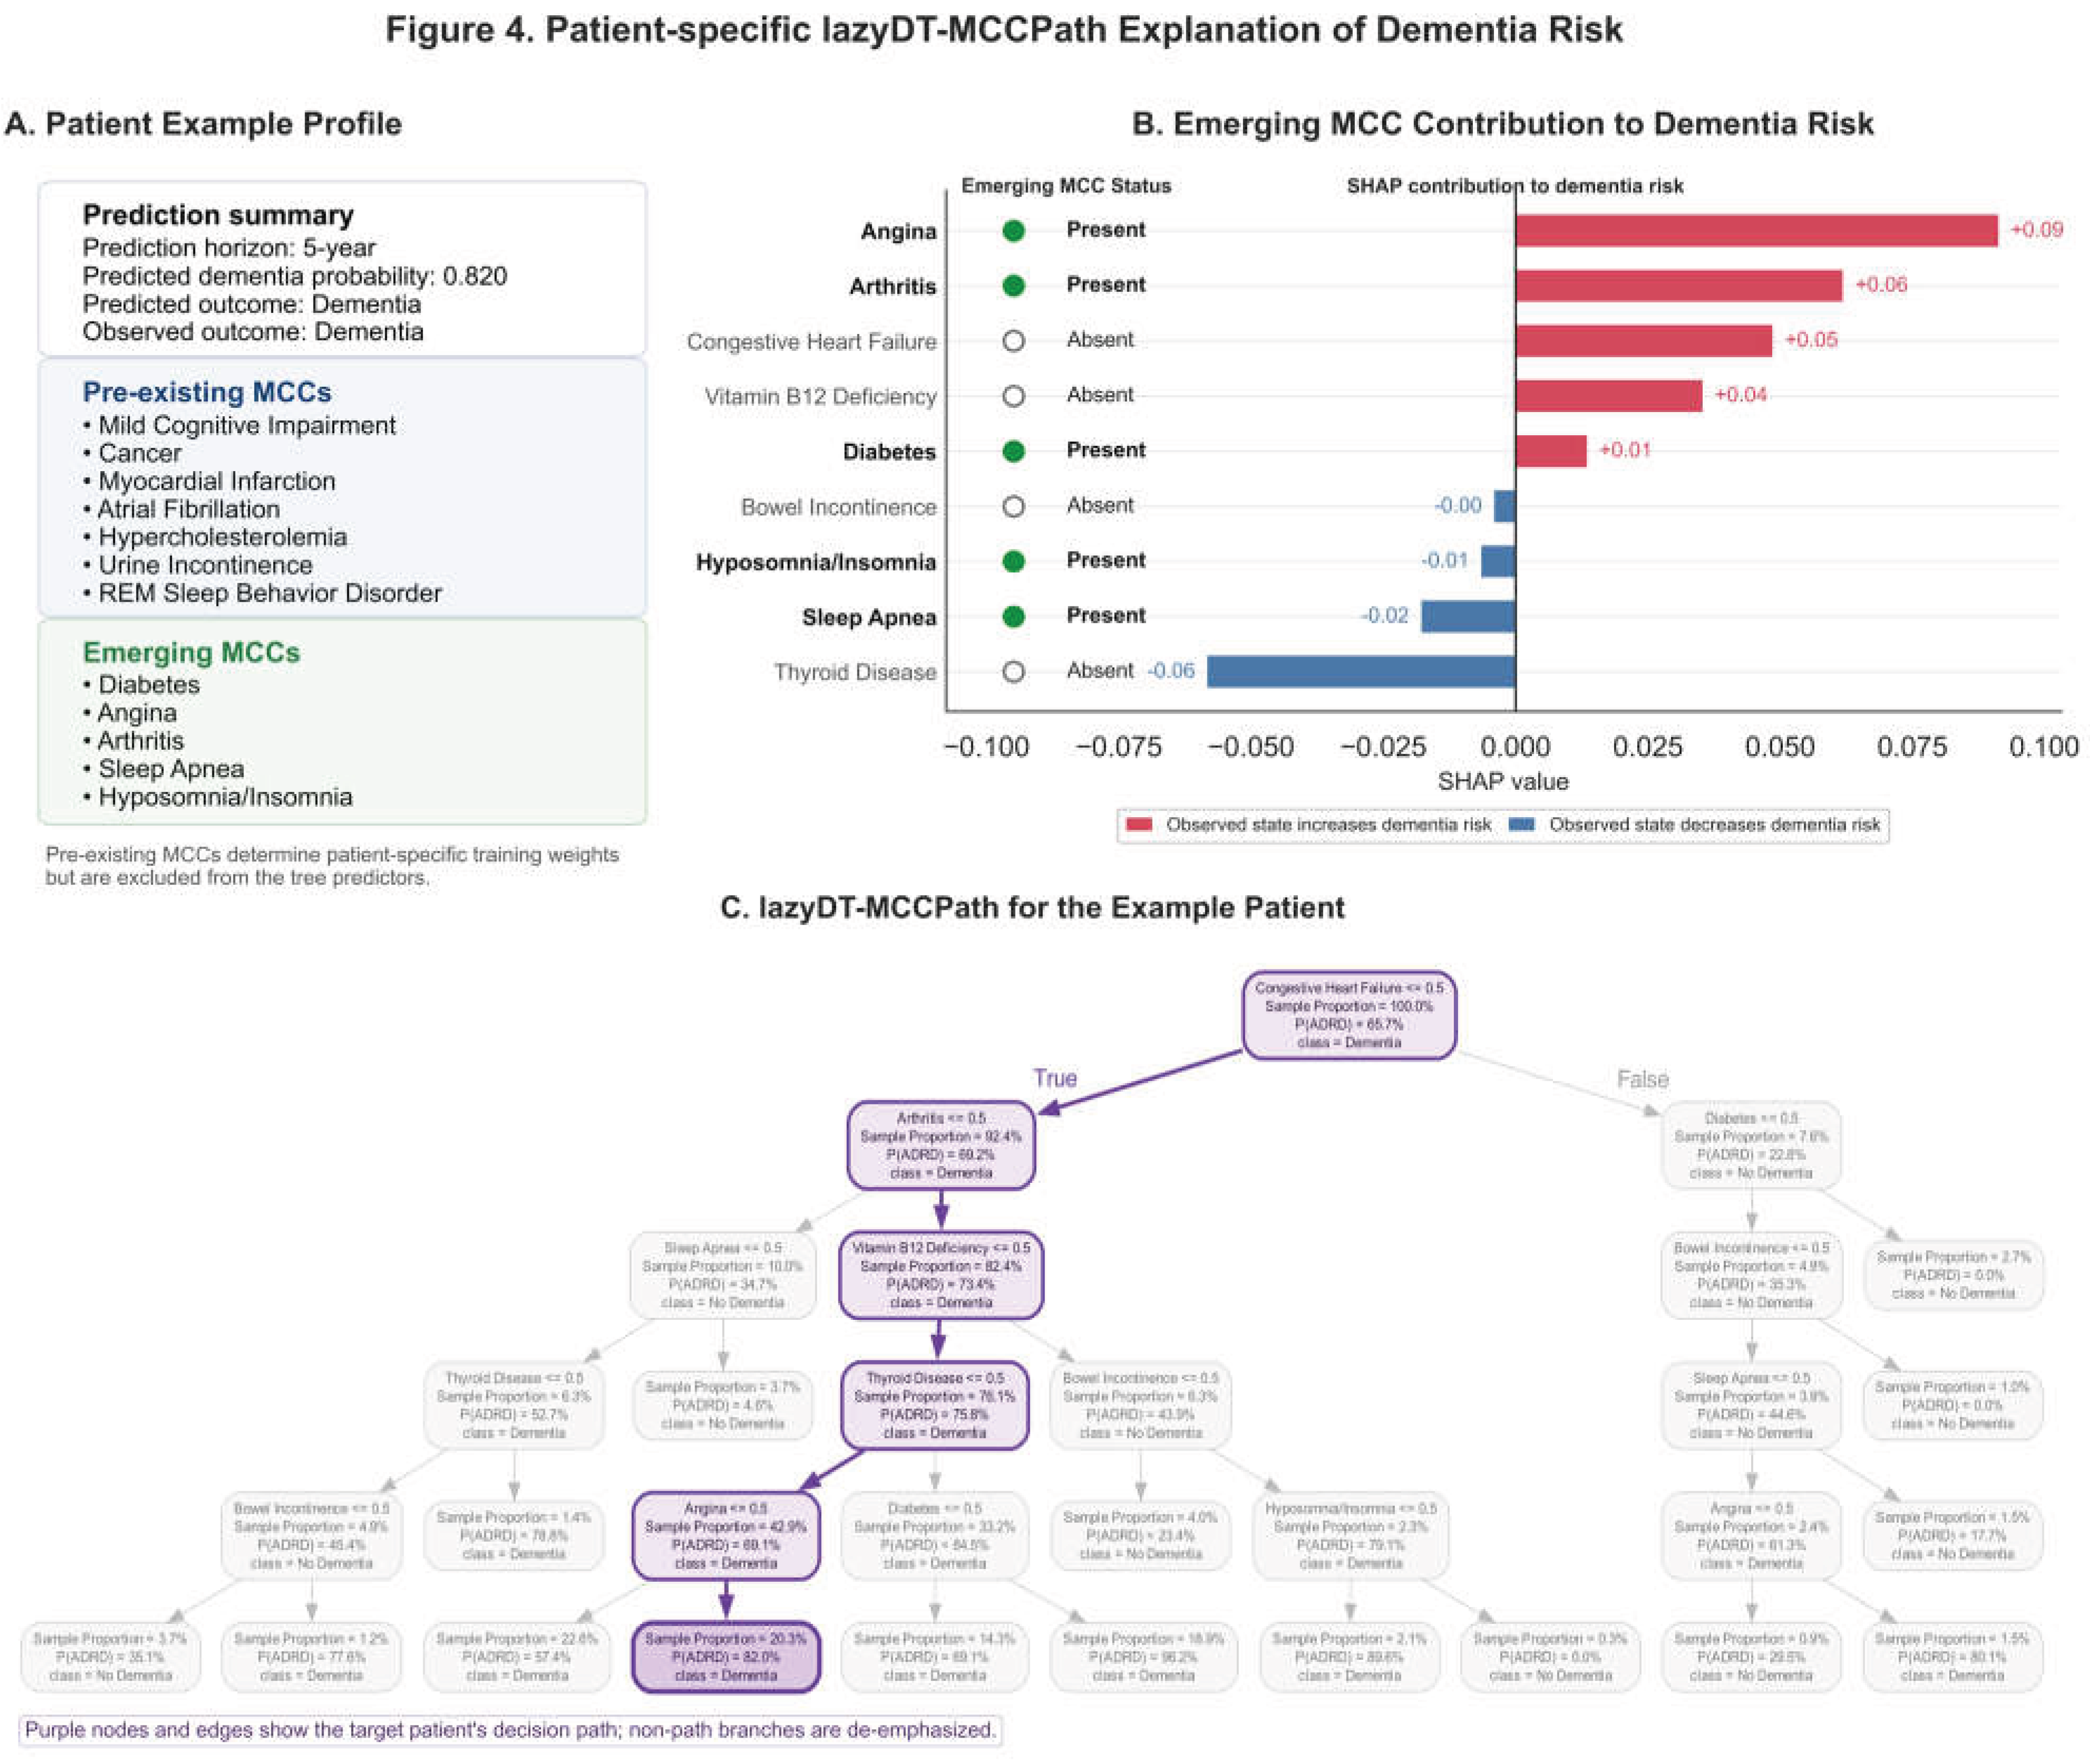

Table 1.
Patient Baseline Characteristics.
| 3-Year Follow-Up | 4-Year Follow-Up | 5-Year Follow-Up | ||||
|
Dementia (n=408) |
No Dementia (n=4972) |
Dementia (n=316) |
No Dementia (n=4189) |
Dementia (n=169) |
No Dementia (n=2969) |
|
| Age, mean (SD) | 79.8 (8.1) | 74.8 (8.9) | 79.2 (8.2) | 73.8 (9.0) | 78.8 (7.6) | 73.6 (8.5) |
| Male, n (%) | 186 (45.6) | 1879 (37.8) | 140 (44.3) | 1577 (37.6) | 74 (43.8) | 1135 (38.2) |
| Female, n (%) | 222 (54.4) | 3093 (62.2) | 176 (55.7) | 2612 (62.4) | 95 (56.2) | 1834 (61.8) |
| Race | ||||||
| White, n (%) | 355 (87.0) | 4088 (82.2) | 273 (86.4) | 3457 (82.5) | 148 (87.6) | 2430 (81.8) |
| Black, n (%) | 39 (9.6) | 654 (13.2) | 33 (10.4) | 537 (12.8) | 15 (8.9) | 394 (13.3) |
| Asian, n (%) | 9 (2.2) | 152 (3.1) | 3 (0.9) | 139 (3.3) | 2 (1.2) | 101 (3.4) |
| Other, n (%) | 5 (1.2) | 78 (1.6) | 7 (2.2) | 56 (1.3) | 4 (2.4) | 44 (1.5) |
| Number of Pre-existing MCCs, mean (SD) | 6.5 (2.1) | 5.2 (2.1) | 6.0 (2.1) | 4.9 (2.0) | 5.7 (2.0) | 4.8 (1.9) |
| Number of Emerging MCCs, mean (SD) | 0.6 (0.9) | 0.5 (0.8) | 1.0 (1.1) | 0.8 (0.9) | 1.3 (1.3) | 1.0 (1.1) |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.