
Submitted:
08 October 2026
Posted:
10 October 2026
You are already at the latest version
Abstract
Background/Objectives: Artificial intelligence (AI) tools for periodontal diagnosis are proliferating, yet little is known about what clinicians and patients in Central Asia expect from such systems. We elicited requirements for an AI-enabled periodontal decision-support system from three stakeholder groups in Kazakhstan and examined which patient-reported risk factors are associated with self-reported signs of periodontal disease. Methods: A cross-sectional online survey (July–September 2026) enrolled 33 dentists, 91 primary health care (PHC) physicians and medical specialists, and 455 patients with periodontal disease. Proportions were reported with Wilson 95% confidence intervals (CI); groups were compared with Fisher’s exact, χ², Mann–Whitney and Kruskal–Wallis tests with effect sizes; multivariable logistic regression identified factors associated with self-reported periodontal signs. Results: Dentists prioritised automation of history-taking (81.8%) and visual gingival assessment (72.7%), and named early gingivitis diagnosis as the stage where AI is most needed (69.7%). Only human-controlled autonomy levels were chosen; the most frequently cited barrier was the absence of a legal framework and liability insurance (60.6%), and dentists with >5 years of experience more often demanded mandatory verification or a prohibition of full autonomy (exact p = 0.045; Cramér’s V = 0.54). PHC physicians considered early gingivitis screening their most effective contribution (80.2%) but cited insufficient competence as the main barrier (53.8%). Self-reported periodontal signs were present in 49.0% of patients and were independently associated with high stress (adjusted odds ratio 2.11; 95% CI 1.14–3.89) and a positive family history (1.61; 1.02–2.55); six symptom items did not form a reliable scale (Cronbach’s α = 0.56). Conclusions: Stakeholders in Kazakhstan favour a low-autonomy, clinician-verified AI system focused on early gingivitis detection, interprofessional data sharing and clearly regulated accountability. These requirements provide an evidence base for the design and governance of periodontal AI in emerging health systems.
Keywords:
artificial intelligence
; periodontal diseases
; clinical decision support systems
; primary health care
; stakeholder survey
; Kazakhstan
; human–AI collaboration
; medical liability
1. Introduction
1.1. The Real-World Problem
Periodontal diseases remain one of the most prevalent chronic conditions of humankind. The World Health Organization (WHO) Global Oral Health Status Report estimated that severe periodontal disease affects about one billion people worldwide [1], and the Global Burden of Disease Study 2021 counted 1.07 billion prevalent cases and 6.9 million disability-adjusted life years, with a projected 40% increase in the number of cases by 2040 driven by population growth and ageing [2]. In Central Asia the age-standardised prevalence of periodontal disease was estimated at 9321 per 100,000 population in 2021 [2]. For Kazakhstan, WHO reported a prevalence of severe periodontal disease of 15.3% among people aged 15 years and older, a dentist density of 2.9 per 10,000 population, and the absence of a national oral health policy or action plan as of 2021 [3]. In a clinic-based study of 642 adults aged 18–80 years attending dental institutions in Astana, the prevalence of inflammatory periodontal diseases increased with age, reaching 99% for gingivitis and 69% for periodontitis in the 66–80-year age group [4]. Periodontitis is also a modifiable contributor to systemic morbidity: consensus reports of the European Federation of Periodontology (EFP) with the International Diabetes Federation and with the World Heart Federation have documented bidirectional links with diabetes mellitus and independent associations with cardiovascular disease [5,6], which cohort meta-analyses confirm (pooled relative risk of periodontitis in people with diabetes 1.24; 95% CI 1.13–1.37) [7]. The 2023 joint workshop of the EFP and the European arm of the World Organization of Family Doctors (WONCA) therefore called for family physicians to screen for periodontal disease and to refer patients with diabetes, cardiovascular and respiratory diseases to dental care [8]. This call resonates with the primary health care (PHC) orientation of the Astana Declaration, adopted in Kazakhstan’s capital in 2018 [9], and with the WHO Global Oral Health Action Plan 2023–2030, which prioritises integration of oral health into PHC and the use of digital technologies [10].
In practice, however, integration of oral health into medical care is hampered by well-documented barriers: limited training of physicians in oral examination, time constraints, unclear referral pathways and the absence of simple screening tools [11]. Surveys of Swiss endocrinologists and general practitioners found that although the diabetes–periodontitis link was widely acknowledged, 34.8% of endocrinologists and 20.4% of general practitioners never or rarely referred patients to a dentist [12], and a survey of primary care physicians in Ireland showed that oral-health recommendations in diabetes guidelines were rarely implemented [13]. In Kazakhstan, where PHC has been substantially reorganised around general practitioners over the past decade, no comparable data exist.
1.2. Current State of the Art
Artificial intelligence (AI) has been proposed as a way to close this diagnostic and interprofessional gap. Deep-learning models detect periodontal bone loss on panoramic radiographs with clinician-level accuracy [14], stage periodontitis automatically [15], and detect gingivitis from smartphone photographs with sensitivity above 90% [16]. Scoping and systematic reviews confirm that most of the evidence base concerns radiographic image analysis, with far fewer studies on clinical decision support, risk prediction from systemic data or remote monitoring [17,18]. A recent systematic scoping review with evidence from Kazakhstan identified two dominant paradigms—image-based deep learning for radiographic bone-loss detection and machine-learning-based non-clinical screening using patient-reported data and salivary biomarkers—documented a consistent drop in performance on external validation, and proposed a phased implementation model for emerging health systems that ends with legal governance covering liability and insurance [19]. Schwendicke et al. emphasised that the “chances” of dental AI will only materialise if problems of data quality, external validation, explainability, regulation and workflow integration are solved [20], and a checklist for the reporting of dental AI research was proposed to raise methodological standards [21]. Ethical analyses have mapped issues of accountability, transparency, autonomy and justice specific to dental AI [22,23], while a framework for medical AI describes a continuum of autonomy levels from human-in-the-loop decision support to fully autonomous systems, each requiring different regulatory safeguards [24]. Explainability, trust and clear allocation of liability are consistently identified as preconditions for clinician acceptance of AI in health care [25,26,27,28].
Empirical evidence on stakeholders’ expectations has accumulated rapidly since 2020, almost exclusively through cross-sectional online questionnaires analysed with descriptive statistics, χ² or Fisher’s exact tests, non-parametric comparisons and, increasingly, ordinal or logistic regression [29]. A survey of 155 Australian dentists and dental students found that 91.6% viewed AI as an assistant to the clinician, with concerns focused on accuracy, insurance liability and lack of transparency [30]. In Bulgaria, 54.7% of 53 dentists preferred clinician-guided AI diagnosis and only 3.8% trusted a fully automated diagnosis [31]. In Kuwait, 300 dental professionals named lack of training (71.2%), technical challenges (63.4%) and cost (56.5%) as the main barriers [32]; in Poland, 183 dentists showed moderate acceptance but almost unanimously rejected AI replacing the dentist [33]; a multi-country survey documented that AI use rises with educational level [34]; and a multicentre study of Egyptian periodontists identified educational gaps as the main determinant of adoption [35]. Questionnaire studies specifically in periodontology report high interest but limited knowledge of AI among dentists in India [36,37]. A multidisciplinary survey in Romania that included dentists, legal professionals and forensic physicians showed that 87.8% would not trust a recommendation whose reasoning could not be verified and 74.0% would refrain from using AI while legal liability remained unclear [38]. Patients, in turn, hold generally positive attitudes towards dental AI but expect the dentist to remain responsible for the decision [39].
1.3. Research Gap
Three gaps are apparent. First, all of the studies cited above originate from high- or upper-middle-income countries in Europe, the Gulf, South Asia and Australia; no study has examined stakeholder expectations of periodontal AI in Central Asia, a region with a high periodontal burden, a comparatively low dentist density and a distinct post-Soviet organisation of dental and medical services. Second, the existing surveys are almost exclusively single-stakeholder: they describe dentists’ attitudes, or patients’ attitudes, but do not triangulate the perspectives of dentists, medical physicians and patients within one study, even though an AI system intended to bridge dental and medical care must satisfy all three. Third, previous work has rarely connected clinicians’ declared data requirements (which comorbidities and risk factors an algorithm should use) with empirical patient-level data on whether those variables are actually associated with periodontal signs in the target population. The regulatory context has also changed: Kazakhstan adopted Central Asia’s first Law “On Artificial Intelligence” (No. 230-VIII of 17 November 2025), which introduces risk-based classification, transparency obligations and mandatory notification of users interacting with AI [40,41], in parallel with the risk-based approach of the European Union AI Act [42] and the WHO guidance on ethics and governance of AI for health [43].
1.4. Objectives
The study therefore had the following objectives: (1) to identify which diagnostic procedures, data inputs, output formats and clinical stages dentists in Kazakhstan prioritise for an AI-enabled periodontal decision-support system, which level of AI autonomy they accept, and which barriers they perceive; (2) to describe how PHC physicians and medical specialists view their own role in periodontal screening, which patient groups they prioritise for AI-assisted screening and which barriers limit oral examination in medical practice; (3) to compare dentists’ and physicians’ opinions on overlapping items; (4) to estimate the prevalence of self-reported signs of periodontal disease among patients and to test the association of these signs with behavioural and systemic risk factors that clinicians proposed as algorithm inputs, including an assessment of whether patient-reported symptom items form a reliable composite scale; and (5) to synthesise the findings into design and governance requirements for periodontal AI in an emerging health system.
2. Materials and Methods
2.1. Study Design and Reporting
We conducted a cross-sectional, questionnaire-based study with three parallel target populations. The design follows the approach used in recent stakeholder surveys on dental AI [32,33,38], which we chose because the research questions concern the distribution of preferences and their association with respondent characteristics at a single time point, for which a cross-sectional survey is the appropriate and most resource-efficient design. Reporting follows the Consensus-Based Checklist for Reporting of Survey Studies (CROSS) [44] and, for the web-based data collection, the Checklist for Reporting Results of Internet E-Surveys (CHERRIES) [45]; the completed CROSS checklist is provided as Supplementary Material S1. The observational elements of the analysis (associations between risk factors and self-reported signs) are reported in accordance with the STROBE recommendations for cross-sectional studies [46].
2.2. Setting and Participants
The study was coordinated by Astana Medical University, Kazakhstan. Three groups were recruited: (1) practising dentists of any specialty; (2) PHC physicians (general practitioners, internists, paediatricians) and medical specialists of somatic profile (endocrinologists, gastroenterologists, cardiologists and others); and (3) adult patients diagnosed with periodontal disease (chronic periodontitis, ICD-10 code K05.4 and related codes) attending dental or PHC facilities. Inclusion criteria were age ≥18 years, current professional activity (for clinicians) and ability to complete an electronic questionnaire in Russian or Kazakh. The protocol foresaw a professional experience of more than five years for dentists and an age above 20 years for patients; because the online forms could not enforce these criteria, respondents outside them were retained and their influence was examined in subgroup and sensitivity analyses (Section 2.8). Recruitment was non-probabilistic: invitations with a link to the electronic form were distributed through professional associations, clinic administrations and the University’s clinical bases in Astana and other regions (Almaty, Aktobe, Turkestan, Karaganda, Shymkent), and patients were invited by their treating clinicians. Participation was voluntary and anonymous.
2.3. Instruments
Three structured questionnaires were developed by a working group of periodontologists, PHC physicians, epidemiologists and a medical informatics specialist, drawing on published instruments on attitudes towards dental AI [30,31] and on the domains of the EFP/WONCA consensus on periodontal–systemic links [8]. Content validity was established through expert review; the forms were piloted with five clinicians and ten patients for clarity and completion time (10–15 min) and revised accordingly. The dentist questionnaire (20 items) covered examination procedures suitable for automation, radiographic and laboratory markers, comorbid and anatomical risk factors, indices difficult to calculate without digital assistance, the clinical stage where AI is most needed, preferred AI functions and output formats, the acceptable level of AI autonomy (five options, all of which left the final decision to the clinician: low autonomy—AI processes data only; medium autonomy—AI proposes options; decision support with mandatory clinician verification; AI as a “second opinion”; full autonomy prohibited), the most important aspect of transparency, criteria of treatment success, barriers to integration, and five open-ended questions. The physician questionnaire (13 items) covered the perceived importance of periodontal status for diabetes control (five-level ordinal item), anamnestic and comorbid factors of severe periodontitis, haematological findings warranting referral to a periodontist, complaints indicative of gingivitis, barriers to oral examination during medical consultations, the stage at which PHC involvement is most effective, and priority groups for AI-assisted screening. The patient questionnaire (20 items) covered gingival bleeding, halitosis, tooth mobility, visual gingival changes, pain, suppuration, xerostomia, symptom duration, oral hygiene habits, smoking, stress, diet, dental attendance, previous periodontal treatment, family history, glycaemic status, cardiovascular and musculoskeletal diseases, and dispensary (registry) status. Most clinician items permitted multiple responses; ordinal patient items had five or six mutually exclusive options ordered by severity. Item wording is provided in Supplementary Material S2.
2.4. Data Collection
Questionnaires were implemented in Google Forms and were open from 27 July to 19 September 2026. Responses were stored without identifiers; IP addresses were not collected. Completion of all closed items was required by the form, so item non-response was limited to “cannot say” options.
2.5. Data Processing
Figure 1 summarises the transition from the raw exports to the analytical samples. Exports were checked for completeness, exact duplicates, logical contradictions and out-of-range values. One exact duplicate was removed from the patient file (456 → 455 records). In the physician file, one respondent’s stated age of 16 years was judged impossible for a practising physician and set to missing (age available for 90 of 91). No records were excluded from the dentist file (n = 33). Each response option of a multiple-choice item was converted into a dichotomous indicator (0 = not selected, 1 = selected); percentages were calculated from the number of respondents and therefore may sum to more than 100% within an item. Six single-choice items in the online forms technically allowed multiple selections (e.g., the frequency of risk re-assessment among dentists and the ordinal item on the importance of periodontal status among physicians); these were analysed as multiple-choice items, and for the ordinal physician item the maximum selected level was additionally derived. Internal inconsistencies in patient records (e.g., “teeth are firm” together with a reported degree of mobility; 62 records with at least one contradiction) were flagged but retained, because they could not be resolved without re-contacting anonymous respondents. Cleaned datasets were stored in SPSS format with a documented codebook (Supplementary Material S3).
2.6. Variables
Ordinal patient responses were scored in increasing order of severity (bleeding 0–5, halitosis 0–4, mobility 0–4, number of pathological gingival signs 0–5, pain 0–5, suppuration 0–4, xerostomia 0–4, stress 0–5, symptom duration 0–5); toothbrushing frequency and dental attendance were reverse-coded so that a higher score denoted a less favourable value throughout. “Cannot say” responses were treated as missing (≤7.5% for any item) and were not imputed. Binary risk-factor indicators were derived as follows: current smoking (any current tobacco use, including heated tobacco), toothbrushing less than twice daily, regular use of interdental aids (floss, mouthwash or interdental brushes), high stress (self-rated high, chronic or depressive level), dysglycaemia (self-reported prediabetes or diabetes; respondents who had never had their glucose measured were kept as a separate category), cardiovascular disease (any reported diagnosis), positive family history of periodontitis or early tooth loss (unknown history kept as a separate category), and dental attendance at least once a year. Professional experience was dichotomised at 5 years for dentists (the protocol’s inclusion threshold) and at 10 years for physicians (the median category). The primary patient outcome was a composite indicator of self-reported signs of periodontal disease, defined a priori as at least one of: gingival bleeding at least when eating hard food, any tooth mobility, at least one visual pathological gingival sign (swelling, redness, recession, ulceration or hyperplasia), or suppuration at least “sometimes on pressure”. This definition follows the logic of the CDC/American Academy of Periodontology self-report items, which combine bleeding, mobility and gum appearance to predict clinically defined periodontitis [47].
2.7. Sample Size Considerations
No formal a priori sample size calculation was performed for the exploratory clinician surveys; all eligible responses received during the study period were analysed. For the patient survey, a sample of 455 provides a margin of error of ±4.6 percentage points for a proportion of 50% at the 95% confidence level, and the 223 outcome events allowed a logistic model with 12 predictor terms while maintaining 18.6 events per variable, above the conventional minimum of 10 [48]. The precision of the clinician estimates is conveyed by the confidence intervals reported with every proportion (half-widths of about ±17 percentage points for n = 33 and ±10 points for n = 91 at p = 50%), and we interpret between-group comparisons in these samples as hypothesis-generating.
2.8. Statistical Analysis
The analytical strategy was chosen to match the measurement level of the data and the small size of the clinician samples, following the practice of comparable published surveys [32,33,38]. Categorical variables are presented as n (%) with 95% confidence intervals (CI) calculated by the Wilson score method, which retains nominal coverage for small samples and proportions near 0 or 100% [49]. The distribution of quantitative variables was assessed with the Shapiro–Wilk test, skewness, kurtosis, histograms and normal Q–Q plots; because no quantitative variable was normally distributed, they are summarised as median [first quartile; third quartile] (Me [Q1; Q3]) and compared with rank-based methods. Two independent groups were compared with the Mann–Whitney U test (asymptotic), with the effect size r = Z/√N and its 95% CI obtained by percentile bootstrap (1000 resamples); three or more groups were compared with the Kruskal–Wallis H test with ε² as effect size. Categorical variables were compared with Pearson’s χ² test; when any expected frequency was below 5, Fisher’s exact test (2 × 2 tables) or its Freeman–Halton extension (2 × k tables) was used, with φ, Cramér’s V and odds ratios (OR) with Woolf 95% CI (0.5 added to all cells in the presence of a zero cell) as effect sizes. Associations between ordinal variables were quantified by Spearman’s rank correlation coefficient (ρ). The internal consistency of the six patient symptom items was examined with Cronbach’s α (95% CI by Feldt’s method), corrected item–total correlations and α-if-item-deleted, with α ≥ 0.70 as the criterion for combining items into a scale. Factors associated with the composite indicator of self-reported periodontal signs were first examined in univariable analyses and then in a multivariable binary logistic regression with simultaneous entry of pre-specified predictors (age per 10 years, sex, smoking status, toothbrushing frequency, use of interdental aids, stress, glycaemic status, cardiovascular disease and family history), categorical predictors being indicator-coded. Model performance was described by the likelihood-ratio χ², Cox–Snell, Nagelkerke and McFadden R², and the area under the receiver operating characteristic curve (AUC); multicollinearity was checked with variance inflation factors (VIF). Because the patient file contained a block of 204 responses received on 2–4 September 2026 with an atypical age structure (190 of them aged 20–22 or 42 years), all principal patient analyses were repeated without this block as a sensitivity analysis. To guard against over-interpretation of the large number of exploratory comparisons among clinicians (69 response options in dentists and 48 in physicians), the number of nominally significant results was compared with the number expected under the global null hypothesis (5% of tests), and results are interpreted as hypotheses rather than confirmatory findings. Two-sided p < 0.05 was considered statistically significant and exact p values are reported. Analyses were performed in IBM SPSS Statistics 27.0 (IBM Corp., Armonk, NY, USA) and Python 3 (pandas, SciPy, statsmodels, pingouin); key statistics were cross-checked between the two environments (Supplementary Material S4).
2.9. Ethics
The study protocol was approved by the Local Bioethics Committee of NJSC “Astana Medical University” (Protocol No. [__] of [date]). The first screen of each electronic form presented the study information and required an affirmative response to an informed-consent statement before the questions were displayed; no personal identifiers were collected.
3. Results
3.1. Characteristics of the Participants
Data from 579 respondents were analysed: 33 dentists, 91 PHC physicians and medical specialists, and 455 patients (Table 1). Dentists were predominantly men (63.6%; 95% CI 46.6–77.8), worked mostly in private clinics (87.9%; 95% CI 72.7–95.2) and in Astana (84.8%); 18 (54.5%) had more than five years of experience. Among physicians, women predominated (86.8%; 95% CI 78.4–92.3); half were general practitioners or internists (50.5%), 17.6% paediatricians, 7.7% endocrinologists and 24.2% other specialists; 72.5% worked in polyclinics, and respondents came from Almaty (44.0%), Astana (30.8%), Aktobe (15.4%) and other cities. Among patients, 67.5% (95% CI 63.0–71.6) were women, 63.3% lived in Astana and 9.2% were on a dispensary register. Age was not normally distributed in any group (Shapiro–Wilk p ≤ 0.011). The age distribution of patients was bimodal, with peaks at 20–22 and 42 years formed by the response block of 2–4 September 2026, whose respondents were younger than the remaining patients (Me 22 [20; 42] vs. 44 [36; 57] years; U = 41,751; p < 0.001; r = 0.55; 95% CI 0.48–0.61).
3.2. Dentists’ Requirements for an AI System
Table 2 summarises the most frequent responses of dentists. The procedures they proposed to automate first were history-taking (81.8%; 95% CI 65.6–91.4) and visual assessment of the gingiva (72.7%; 95% CI 55.8–84.9), and on panoramic radiographs the destruction of the cortical plate of the interdental septa (90.9%; 95% CI 76.4–96.9). Early diagnosis of gingivitis was the stage at which AI was considered most needed (69.7%), followed by differential diagnosis of mild versus moderate periodontitis (60.6%) and screening of healthy individuals (57.6%). Diabetes mellitus (81.8%) and the quality of individual oral hygiene (84.8%) were the systemic and behavioural inputs most often proposed for the algorithm; remote monitoring (66.7%), photograph-based index calculation (60.6%) and prediction of tooth loss (57.6%) were the preferred functions; and a graphical periodontal chart with colour-coded risk zones was the preferred output (66.7%). A reduction in probing depth (75.8%) and stabilisation of the interdental septal height (69.7%) were the most frequently chosen criteria of treatment success.
Responses on the acceptable level of AI autonomy were distributed without a clear majority: low autonomy, in which AI only processes data and the choice remains with the clinician, was selected most often (30.3%; 95% CI 17.4–47.3), and each of the remaining options by 15.2–18.2%. Notably, every option in this item preserved clinician control over the decision, and the open-ended answers on responsibility were nearly unanimous that “the final decision is always the doctor’s”. The most frequently reported barrier to integrating AI into daily work was the absence of a legal framework and liability insurance (60.6%; 95% CI 43.7–75.3), followed by a complex interface requiring IT skills (54.5%), high workload (51.5%) and distrust of automated diagnostic output (51.5%), whereas equipment incompatibility (27.3%) and cost (30.3%) were cited less often (Figure 2a). The confidence intervals of the four leading barriers overlap, so their rank order cannot be established from these data.
The choice of autonomy level differed by professional experience (Table 3; Figure 2b). Dentists with ≤5 years of experience more often chose low autonomy (46.7% vs. 16.7%), whereas those with >5 years more often chose decision support with mandatory verification (27.8% vs. 6.7%) or the option “full autonomy prohibited, the choice is always the doctor’s” (27.8% vs. 0.0%) (Fisher–Freeman–Halton exact p = 0.045; Cramér’s V = 0.54). The same group more often considered the delimitation of responsibility between clinician and AI to be the most important aspect of transparency (50.0% vs. 6.7%; exact p = 0.012; V = 0.60), whereas less experienced dentists prioritised seeing the source data (53.3% vs. 22.2%). Although the V values indicate strong associations, the subgroups comprised only 15 and 18 respondents. Of 69 response options in the multiple-choice items, 7 differed by experience at p < 0.05 (Supplementary Table S1), about twice the 3.5 expected by chance; six of them were selected more often by experienced dentists (e.g., crowding as an anatomical risk factor, 94.4% vs. 46.7%; furcation involvement on radiographs, 77.8% vs. 26.7%), and only distrust of automated results was more frequent among less experienced dentists (73.3% vs. 33.3%; OR 0.18; 95% CI 0.04–0.82; p = 0.037). The total number of options selected was higher among experienced dentists (Me 43.0 [36.8; 51.3] vs. 31.0 [25.5; 41.5]) without reaching significance (U = 86.5; p = 0.079; r = 0.31).
3.3. Views of PHC Physicians and Medical Specialists
Almost half of the physicians (46.2%; 95% CI 36.3–56.3) rated periodontal status as “extremely critical” for the compensation of diabetes, and the median of the maximum selected level was 4 [3,5] on a five-point scale (Table 4). Severe periodontitis was most often linked to the duration of the underlying systemic disease (75.8%) and the duration of smoking (67.0%); gastrointestinal diseases (67.0%) and diabetes (62.6%) were the comorbidities proposed for automatic AI alerts about the risk of tooth loss; and gingival bleeding was recognised as an early sign by 76.9%. Physicians identified early screening for gingivitis as the stage at which their own contribution would be most effective (80.2%; 95% CI 70.9–87.1) and patients with diabetes as the priority group for AI-assisted screening (71.4%), followed by adults aged ≥65 years (62.6%). The main obstacles to examining the oral cavity during a medical consultation were insufficient competence in periodontal assessment (53.8%), low patient motivation (51.6%), lack of time (42.9%) and the absence of simple tools such as an AI-based scanner (41.8%); 35.2% considered it the dentist’s responsibility (Figure 3). Asked which single indicator would best capture the impact of periodontitis on quality of life and disability-adjusted life years, physicians most often chose emergency visits (33.0%) and economic costs (24.2%).
The rating of criticality did not differ by specialty (Kruskal–Wallis H(3) = 4.69; p = 0.196; ε² = 0.052) or by experience (≤10 vs. >10 years; U = 913.0; p = 0.783; r = 0.03), and endocrinologists chose “extremely critical” no more often than other specialists (3/7 vs. 39/84; Fisher’s exact p = 1.000). The total number of selected options, however, differed by specialty (H(3) = 13.44; p = 0.004; ε² = 0.149): paediatricians selected more options than general practitioners (Me 37 vs. 21; U = 139.5; p < 0.001; r = 0.47; 95% CI 0.25–0.66) and than other specialists (p = 0.004; r = 0.47), which probably reflects response style rather than substantive disagreement, since 9 of 16 paediatricians responded within a single hour on one day. Of 48 response options compared by experience, only one differed at p < 0.05 (discomfort on chewing as a sign of gingivitis: 49.2% vs. 25.0%; OR 2.90; 95% CI 1.12–7.49; p = 0.028), consistent with the 2.4 chance findings expected.
3.4. Dentists versus Physicians
Nine items were comparable between the two clinician questionnaires (Table 5; Figure 4). The groups did not differ significantly in the comorbidities they wished the algorithm to consider (all p ≥ 0.052), the largest discrepancy concerning diabetes, which dentists selected more often (81.8% vs. 62.6%; p = 0.052; φ = 0.18). Both groups placed early diagnosis or screening of gingivitis first (69.7% vs. 80.2%; p = 0.231), but dentists more often saw a role for AI in monitoring stabilisation during remission (54.5% vs. 27.5%; OR 3.17; 95% CI 1.39–7.23; p = 0.010; φ = 0.25). Given 33 dentists, the power of these comparisons is limited, and the absence of significant differences should not be read as agreement.
3.5. Patients: Self-Reported Signs and Associated Factors
Gingival bleeding was the most frequent sign among patients: 71.4% reported it at least occasionally and 15.8% daily or more often; 68.0% of those able to answer reported halitosis. Less frequent were at least one visual pathological gingival sign (30.3%), pain (21.8%), tooth mobility (20.4%) and suppuration including a single episode (10.3%), whereas 253 respondents (55.6%) stated that they had had no symptoms of gum disease (Supplementary Table S2 gives the descriptive statistics of all ordinal items). Behaviourally, 69.9% brushed at least twice daily, 60.9% used interdental aids, 23.3% were current or former smokers and 13.6% reported high chronic stress or depression; 7.0% reported dysglycaemia (prediabetes 4.6%, diabetes 2.4%), 14.1% cardiovascular disease and 28.4% a positive family history.
The six symptom items did not form a reliable composite scale: Cronbach’s α = 0.56 (95% CI 0.48–0.62; standardised α = 0.57; n = 399 with complete answers), corrected item–total correlations ranged from 0.19 to 0.38, deleting any item did not raise α above 0.55, and α remained below 0.70 without the 2–4 September block (0.62; 95% CI 0.54–0.70) (Supplementary Table S3). Symptoms were therefore analysed individually and through the pre-specified composite indicator, which was positive in 223 of 455 patients (49.0%; 95% CI 44.5–53.6).
In univariable analyses (Table 6), self-reported signs were more frequent in patients with high stress (69.4% vs. 45.8%; OR 2.68; 95% CI 1.51–4.76), dysglycaemia (75.0% vs. 46.0%; OR 3.52; 95% CI 1.55–8.04), cardiovascular disease (70.3% vs. 45.5%; OR 2.83; 95% CI 1.60–5.02) and a positive family history (61.2% vs. 42.1%; OR 2.17; 95% CI 1.41–3.34), whereas sex, current smoking, brushing frequency and regular dental attendance were not associated with the indicator; all φ coefficients were ≤0.18. The proportion with signs rose with age but not monotonically (41.4%, 45.3%, 67.6% and 58.3% in the 18–29, 30–44, 45–59 and ≥60-year groups; χ²(3) = 16.34; p < 0.001; V = 0.19; Figure 5a). At the level of individual symptoms, 27 of 56 factor–symptom comparisons reached p < 0.05, always in the direction of higher symptom scores in the presence of the factor; a positive family history was associated with all seven symptoms (r = 0.15–0.30) and high stress with six of seven, while current smoking was associated with halitosis, pain, suppuration and xerostomia but not with bleeding (r = 0.00; p = 0.976) (Supplementary Table S4). Spearman correlations between symptoms, age and behaviours were all weak (|ρ| ≤ 0.37; Supplementary Figure S1); brushing frequency correlated with dental attendance (ρ = 0.32; p < 0.001) but not with bleeding (ρ = 0.08; p = 0.099).
In the multivariable model (Table 7; Figure 5b), high stress (adjusted OR 2.11; 95% CI 1.14–3.89; p = 0.017) and a positive family history (adjusted OR 1.61; 95% CI 1.02–2.55; p = 0.043) remained independently associated with self-reported signs, whereas dysglycaemia (adjusted OR 2.02; 95% CI 0.81–5.04) and cardiovascular disease (1.72; 0.89–3.34) retained the direction but not the significance of their univariable associations after adjustment for age and the other predictors. The model was significant (χ²(12) = 44.11; p < 0.001) but explained a small share of the variance (Nagelkerke R² = 0.12) with limited discrimination (AUC = 0.665); VIF ranged from 1.04 to 1.37 and there were 18.6 events per predictor.
3.6. Sensitivity Analysis
Without the 2–4 September response block (n = 251; 140 events), the model remained significant (χ²(12) = 25.29; p = 0.014; Nagelkerke R² = 0.128; AUC = 0.674) and all effects kept their direction, but no predictor reached significance (high stress: OR 1.73; 95% CI 0.78–3.85; family history: 1.52; 0.82–2.81; age per 10 years: 1.23; 0.99–1.52; p = 0.059). The estimates of the main model are therefore sensitive to the exclusion of this block, and the data cannot distinguish whether this reflects the composition of the block or the loss of statistical power.
4. Discussion
4.1. Principal Findings
This is, to our knowledge, the first study from Central Asia to elicit requirements for periodontal AI simultaneously from dentists, medical physicians and patients. Four findings stand out. First, dentists want AI to support the earliest and most frequent tasks of periodontal care—history-taking, visual gingival assessment and early gingivitis detection—rather than the advanced radiographic staging on which most of the technical literature has concentrated [17,18]. Second, no dentist chose an autonomy level that removed the clinician from the decision, and the leading barrier was legal rather than technical: the absence of a liability framework outranked interface complexity, workload, cost and equipment. Dentists with more than five years of experience were particularly likely to demand mandatory verification or a formal prohibition of full autonomy and to define transparency as a clear delimitation of responsibility. Third, PHC physicians and specialists recognised periodontal status as critical for diabetes control, saw early gingivitis screening as their most effective contribution and prioritised patients with diabetes and older adults, but more than half acknowledged insufficient competence to examine the periodontium. Fourth, among patients, self-reported periodontal signs were common (49.0%) and independently associated with high stress and a positive family history, while the associations with dysglycaemia and cardiovascular disease that clinicians expected were present in univariable analysis but attenuated after adjustment, and the symptom items did not form a reliable scale.
4.2. Autonomy, Accountability and Trust in International Perspective
The preference for clinician-controlled AI in Kazakhstan mirrors findings from very different health systems. In Bulgaria, 54.7% of dentists preferred clinician-guided diagnosis and only 3.8% trusted a fully automated diagnosis [31]; in Australia, 91.6% of dentists and students regarded AI as an assistant and named insurance liability and lack of transparency among their principal concerns [30]; in Poland, acceptance of AI replacing the dentist was almost nil (2.7%) despite moderate overall acceptance [33]; and a systematic review of 13 studies concluded that dentists consistently frame AI as a supplementary tool [29]. The Romanian multi-stakeholder survey provides the closest parallel to our liability finding: 74.0% of respondents would refrain from using AI while legal liability remained unclear, 87.8% would not trust an unverifiable recommendation, and responsibility was attributed primarily to clinicians (77.4%) [38]. Our open-ended responses were strikingly similar—”the responsibility lies entirely with the doctor”—with a minority suggesting shared responsibility with developers, an allocation that legal scholarship has long identified as unresolved [28]. What differs is the ranking of barriers. In Kuwait, lack of training (71.2%), technical challenges (63.4%) and cost (56.5%) dominated [32], and in Egypt educational gaps were the main determinant of adoption among periodontists [35], whereas in our sample the legal vacuum came first and cost and equipment last. A plausible explanation is timing: our survey was conducted within a year of the adoption of Kazakhstan’s Law “On Artificial Intelligence”, which introduced risk-based classification, transparency and user-notification obligations but does not yet specify the allocation of clinical liability or the procedures for approving AI as a medical device [40,41]. The salience of regulation among our respondents may therefore reflect an awareness of unfinished regulatory work rather than a cultural peculiarity, much as the risk-based obligations of the European Union AI Act [42] and the WHO governance principles [43] have shaped the discourse elsewhere.
The experience gradient we observed—younger dentists preferring “low autonomy” defined as AI processing data only, older dentists preferring explicit verification rules and formal prohibition of full autonomy—has not been reported in this form before, although age and experience have been associated with attitudes in several surveys, in inconsistent directions [29,33]. One interpretation, consistent with the framework of autonomy levels proposed by Bitterman et al. [24], is that experienced clinicians reason about AI in terms of accountability structures (who verifies, who is liable), whereas less experienced clinicians reason in terms of the technical scope of the tool. Younger dentists were also more likely to distrust automated output (73.3% vs. 33.3%), which contrasts with the higher AI use reported among younger and more highly educated dental professionals elsewhere [34] and suggests that in Kazakhstan familiarity with AI is not yet stratified by age. These subgroup results rest on 15 and 18 respondents and must be replicated.
4.3. The Role of Primary Care
The physicians’ responses reproduce the international pattern of high awareness but limited practice. In Switzerland, all surveyed endocrinologists and general practitioners recognised periodontitis as inflammatory and 82.6% linked poor glycaemic control to severe periodontal disease, yet 34.8% and 20.4% respectively never or rarely referred patients to a dentist, citing insufficient training and time [12]; Irish primary care physicians rarely implemented oral-health recommendations for diabetes [13]; and a scoping review of the integration of oral health into primary care identified competence, time, reimbursement and the lack of simple tools as recurrent barriers [11]. Our respondents named exactly these barriers—competence (53.8%), patient motivation (51.6%), time (42.9%) and the absence of a simple instrument (41.8%)—while simultaneously endorsing early gingivitis screening as their most effective contribution (80.2%). This combination is an argument for a specific product: a low-threshold AI screening tool for the PHC consultation that does not require periodontal expertise, for example smartphone-photograph analysis, whose sensitivity for gingivitis has exceeded 90% in validation studies [16], or a short validated self-report instrument such as the rapid periodontitis screening tool developed for medical settings [50]. Such a tool would operationalise the EFP/WONCA recommendation that family physicians screen and refer [8] and the WHO action-plan target of integrating oral health into PHC [10]. The convergence of dentists and physicians on early gingivitis as the priority stage, and their agreement on diabetes as the key comorbidity, indicate that a shared data model between dental and medical records is feasible; the dentists’ open-ended answers explicitly requested “one database” and a dashboard visible to all treating clinicians.
4.4. Patient-Level Evidence for Algorithm Inputs
Clinicians proposed diabetes, oral hygiene and smoking as the principal inputs for a periodontal algorithm. Our patient data partly support and partly qualify this. The univariable association between dysglycaemia and self-reported signs (OR 3.52) is consistent with the established bidirectional relationship [5,7,51], and the association with cardiovascular disease (OR 2.83) with the EFP/World Heart Federation consensus [6]; the attenuation of both after adjustment for age is expected given the small number of affected patients (32 with dysglycaemia, 64 with cardiovascular disease) and the correlation of both conditions with age. The independent association with high stress (adjusted OR 2.11) agrees with meta-analytic evidence that psychological stress is associated with periodontitis [52] and with the psychobiological pathways described for stress-related diseases and periodontal wound healing [53]; the association with a positive family history (adjusted OR 1.61) is in line with a systematic review estimating that up to a third of the population variance in periodontitis is attributable to genetic factors, with higher estimates for severe forms [54]. By contrast, current smoking was not associated with the composite indicator or with bleeding, despite the well-established effect of smoking on periodontitis (pooled relative risk about 1.85) [55]. This apparent contradiction is best explained by the composition of the outcome: smoking suppresses gingival bleeding through vasoconstriction, so a self-reported indicator dominated by bleeding is expected to be insensitive in smokers, whereas smoking was clearly associated with halitosis, suppuration and xerostomia in our data. Similarly, toothbrushing frequency and dental attendance were unrelated to self-reported signs; brushing correlated with attendance but not with bleeding, which suggests that in this sample hygiene behaviour indexes health consciousness more than plaque control. For algorithm design, these results imply that stress and family history—variables that clinicians did not rank highly (stress was proposed by 42.4% of dentists and 34.1% of physicians, heredity by 44.0% of physicians)—deserve inclusion, and that self-reported bleeding should be complemented by other symptoms in smokers.
The low internal consistency of the six symptom items (α = 0.56) is itself informative. The CDC/American Academy of Periodontology self-report items predicted clinically defined periodontitis with an AUC of 0.81–0.82 in a large United States sample [47], and validated rapid screening instruments exist for medical settings [50]. Our ad hoc items, which mix frequency, severity and appearance across different response formats, do not reach this standard, and our composite indicator should be regarded as a pragmatic outcome rather than a validated measure. An AI system that relies on patient-reported data will need locally validated instruments in Russian and Kazakh.
4.5. Implications for the Design and Governance of Periodontal AI
Table 8 translates the findings into requirements. Functionally, stakeholders converge on early detection of gingivitis, structured history-taking, photograph-based assessment and remote monitoring, with a graphical periodontal chart as the primary output and an ICD-coded text summary as a secondary one. Architecturally, the system should ingest systemic data (glycaemic status, cardiovascular disease, stress, family history, smoking) and support interprofessional access. In terms of human–AI interaction, the acceptable design corresponds to the lowest autonomy levels described by Bitterman et al. [24]: AI proposes, the clinician verifies and decides, and the interface exposes the source data (the transparency element prioritised by younger dentists) and the allocation of responsibility (prioritised by experienced dentists), in keeping with the transparency and explainability requirements of the ethical frameworks for dental AI [22,23,25]. Governance-wise, the study identifies the clarification of liability and insurance under the new national AI law and the health-care legislation as a precondition for adoption, echoing the observation that trust in health-care AI depends on institutional as much as on technical assurances [26,27]. This requirement corresponds to the final stage—legal governance covering liability and insurance—of the phased implementation model proposed for periodontal AI in Kazakhstan [19].
4.6. Strengths and Limitations
The strengths of the study are the triangulation of three stakeholder groups within a single framework, the comparatively large patient sample, the transparent documentation of data processing (Figure 1) and codebooks, the systematic use of confidence intervals and effect sizes, the explicit accounting for multiple exploratory comparisons, and the pre-specified sensitivity analysis. Several limitations must be acknowledged. The cross-sectional design precludes causal inference. Periodontal status was self-reported without clinical indices; more than half of the patients denied any symptoms despite a recorded diagnosis, which may reflect successful treatment, low symptom awareness or imprecise application of the inclusion criterion, and the composite indicator is not a validated instrument. Sampling was non-probabilistic: dentists were mostly private practitioners from Astana, endocrinologists, gastroenterologists and haematologists were few, and the response rate cannot be calculated. The inclusion criteria were not fully enforced (15 dentists had ≤5 years of experience and 82 patients were aged ≤20 years), and blocks of responses received within short periods showed homogeneous age structures or response styles; although the sensitivity analysis preserved the direction of all effects, it removed their statistical significance, so the patient-level associations are preliminary. Six single-choice items in the online forms allowed multiple selections, and the option sets differed slightly from the approved paper versions. The questionnaires did not include validated scales of AI knowledge, experience or readiness, and the small dentist sample (n = 33) limits the power of all clinician comparisons; the associations with professional experience in particular rest on subgroups of 15 and 18 respondents. Finally, most effect sizes among patients were small (φ ≤ 0.18; r ≤ 0.30; |ρ| ≤ 0.37), and the multivariable model explained only about 12% of the variance, so the identified factors are candidate inputs rather than a predictive model. A comparable limitation was observed in a five-year analysis of emergency medical service data from Astana, in which routinely coded cardiac comorbidities were independently associated with the prehospital transport decision, but the model achieved only moderate discrimination (AUC 0.69) and was not recommended for individual triage without prospective validation and additional clinical data [56].
4.7. Future Research
The requirements identified here should be tested by developing a prototype decision-support tool for the PHC setting and evaluating its accuracy against clinical periodontal examination, its acceptability under different autonomy configurations, and its effect on referral behaviour. Validation of Russian- and Kazakh-language self-report instruments against clinical indices, a probability-based survey of dentists across regions of Kazakhstan with validated attitude scales, and comparative analyses with neighbouring Central Asian countries would strengthen the evidence base. Qualitative work with regulators, insurers and developers is needed to translate the demand for liability rules into concrete provisions under the national AI law.
5. Conclusions
Dentists, primary care physicians and patients in Kazakhstan articulate a coherent set of expectations for periodontal AI: a clinician-verified, low-autonomy system that supports early gingivitis detection, structured data collection and interprofessional communication, presents its output as a graphical periodontal chart, and operates within a clear legal allocation of responsibility. Physicians are willing to screen for gingivitis but need a tool that compensates for their limited periodontal training. Patient-level data support the inclusion of stress and family history alongside the metabolic and cardiovascular variables that clinicians expected, while highlighting the need for validated self-report instruments. Because Kazakhstan has just adopted its first AI law, the study’s central message is that the adoption of periodontal AI in this setting will depend on the regulatory delimitation of accountability at least as much as on technical readiness.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/[doi]/s1. Supplementary Material S1: CROSS checklist; S2: questionnaires (English translation); S3: codebooks of the three datasets; S4: cross-validation of statistics between SPSS and Python; Table S1: response options of dentists differing by professional experience; Table S2: descriptive statistics of ordinal patient items; Table S3: item characteristics of the candidate symptom scale; Table S4: symptom scores by risk factor (effect size r); Table S5: symptom scores by age group and smoking status (Kruskal–Wallis); Figure S1: Spearman correlation matrix.
Author Contributions
Conceptualization, A.I. and A.M.; methodology, A.Zh.; software, Y.A.; validation, A.A.; formal analysis, A.Zh., A.C.; investigation, A.M., Y.A.; resources, Y.A.; data curation, Y.A., A.Zh., A.C.; writing—original draft preparation, A.C.; writing—review and editing, Y.A., A.Zh., A.C, A.A.; visualization, A.C.; supervision, A.M.; project administration, A.M., A.C.; funding acquisition, Y.A.. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Local Bioethics Committee of NJSC “Astana Medical University” (Protocol No.1/ID:312, 24.06.2026y.).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study through an electronic consent statement preceding the questionnaire.
Data Availability Statement
The anonymised datasets and analysis code supporting the findings of this study are available from the corresponding author on reasonable request.
Acknowledgments
The authors thank the participating clinics, professional associations and respondents.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| AI | Artificial intelligence |
| aOR | Adjusted odds ratio |
| AUC | Area under the receiver operating characteristic curve |
| CDSS | Clinical decision-support system |
| CHERRIES | Checklist for Reporting Results of Internet E-Surveys |
| CI | Confidence interval |
| CPITN | Community Periodontal Index of Treatment Needs |
| CROSS | Consensus-Based Checklist for Reporting of Survey Studies |
| EFP | European Federation of Periodontology |
| ESR | Erythrocyte sedimentation rate |
| ICD-10 | International Classification of Diseases, 10th Revision |
| IL | Interleukin |
| Me | Median |
| OR | Odds ratio |
| PHC | Primary health care |
| PMA | Papillary–marginal–alveolar index |
| Q1, Q3 | First and third quartiles |
| SE | Standard error |
| STROBE | Strengthening the Reporting of Observational Studies in Epidemiology |
| VIF | Variance inflation factor |
| WHO | World Health Organization |
| WONCA | World Organization of Family Doctors |
References
- World Health Organization. Global Oral Health Status Report: Towards Universal Health Coverage for Oral Health by 2030; World Health Organization: Geneva, Switzerland, 2022; Available online: https://www.who.int/publications/i/item/9789240061484 (accessed on 29 September 2026).
- Hu, M.; Zhang, R.; Wang, R.; Wang, Y.; Guo, J. Global, regional, and national burden of periodontal diseases from 1990 to 2021 and predictions to 2040: An analysis of the Global Burden of Disease Study 2021. Front. Oral Health 2025, 6, 1627746. [Google Scholar] [CrossRef]
- World Health Organization. Oral Health Kazakhstan 2022 Country Profile; World Health Organization: Geneva, Switzerland, 2022; Available online: https://www.who.int/publications/m/item/oral-health-kaz-2022-country-profile (accessed on 29 September 2026).
- Onerova, A.; Yeslyamgaliyeva, A. Prevalence of inflammatory periodontal diseases. Przegl. Epidemiol. 2024, 78, 182–192. [Google Scholar] [CrossRef]
- Sanz, M.; Ceriello, A.; Buysschaert, M.; Chapple, I.; Demmer, R.T.; Graziani, F.; Herrera, D.; Jepsen, S.; Lione, L.; Madianos, P.; et al. Scientific evidence on the links between periodontal diseases and diabetes: Consensus report and guidelines of the joint workshop on periodontal diseases and diabetes by the International Diabetes Federation and the European Federation of Periodontology. J. Clin. Periodontol. 2018, 45, 138–149. [Google Scholar] [CrossRef]
- Sanz, M.; Marco del Castillo, A.; Jepsen, S.; Gonzalez-Juanatey, J.R.; D’Aiuto, F.; Bouchard, P.; Chapple, I.; Dietrich, T.; Gotsman, I.; Graziani, F.; et al. Periodontitis and cardiovascular diseases: Consensus report. J. Clin. Periodontol. 2020, 47, 268–288. [Google Scholar] [CrossRef]
- Stöhr, J.; Barbaresko, J.; Neuenschwander, M.; Schlesinger, S. Bidirectional association between periodontal disease and diabetes mellitus: A systematic review and meta-analysis of cohort studies. Sci. Rep. 2021, 11, 13686. [Google Scholar] [CrossRef]
- Herrera, D.; Sanz, M.; Shapira, L.; Brotons, C.; Chapple, I.; Frese, T.; Graziani, F.; Hobbs, F.D.R.; Huck, O.; Hummers, E.; et al. Association between periodontal diseases and cardiovascular diseases, diabetes and respiratory diseases: Consensus report of the Joint Workshop by the European Federation of Periodontology (EFP) and the European arm of the World Organization of Family Doctors (WONCA Europe). J. Clin. Periodontol. 2023, 50, 819–841. [Google Scholar] [CrossRef]
- World Health Organization; United Nations Children’s Fund. Declaration of Astana: Global Conference on Primary Health Care, Astana, Kazakhstan, 25–26 October 2018; World Health Organization: Geneva, Switzerland, 2018; Available online: https://www.who.int/publications/i/item/WHO-HIS-SDS-2018.61 (accessed on 29 September 2026).
- World Health Organization. Global Strategy and Action Plan on Oral Health 2023–2030; World Health Organization: Geneva, Switzerland, 2024; Available online: https://www.who.int/publications/i/item/9789240090538 (accessed on 29 September 2026).
- Harnagea, H.; Couturier, Y.; Shrivastava, R.; Girard, F.; Lamothe, L.; Bedos, C.P.; Emami, E. Barriers and facilitators in the integration of oral health into primary care: A scoping review. BMJ Open 2017, 7, e016078. [Google Scholar] [CrossRef]
- Chatzaki, N.; Zekeridou, A.; Paroz, E.; Gastaldi, G.; Giannopoulou, C. Knowledge and practice attitudes regarding the relationship between diabetes and periodontitis: A survey among Swiss endocrinologists and general physicians. BMC Prim. Care 2023, 24, 238. [Google Scholar] [CrossRef]
- Ahern, J.; Nunn, J. The integration of oral health-related best practice recommendations in the management of patients with diabetes: A cross-sectional survey of primary care physicians. J. Public Health Dent. 2021, 81, 245–248. [Google Scholar] [CrossRef]
- Krois, J.; Ekert, T.; Meinhold, L.; Golla, T.; Kharbot, B.; Wittemeier, A.; Dörfer, C.; Schwendicke, F. Deep learning for the radiographic detection of periodontal bone loss. Sci. Rep. 2019, 9, 8495. [Google Scholar] [CrossRef]
- Chang, H.J.; Lee, S.J.; Yong, T.H.; Shin, N.Y.; Jang, B.G.; Kim, J.E.; Huh, K.H.; Lee, S.S.; Heo, M.S.; Choi, S.C.; et al. Deep learning hybrid method to automatically diagnose periodontal bone loss and stage periodontitis. Sci. Rep. 2020, 10, 7531. [Google Scholar] [CrossRef]
- Chau, R.C.W.; Li, G.H.; Tew, I.M.; Thu, K.M.; McGrath, C.; Lo, W.L.; Ling, W.K.; Hsung, R.T.C.; Lam, W.Y.H. Accuracy of artificial intelligence-based photographic detection of gingivitis. Int. Dent. J. 2023, 73, 724–730. [Google Scholar] [CrossRef]
- Mohammad-Rahimi, H.; Motamedian, S.R.; Pirayesh, Z.; Haiat, A.; Zahedrozegar, S.; Mahmoudinia, E.; Rohban, M.H.; Krois, J.; Lee, J.H.; Schwendicke, F. Deep learning in periodontology and oral implantology: A scoping review. J. Periodontal Res. 2022, 57, 942–951. [Google Scholar] [CrossRef]
- Revilla-León, M.; Gómez-Polo, M.; Barmak, A.B.; Inam, W.; Kan, J.Y.K.; Kois, J.C.; Akal, O. Artificial intelligence models for diagnosing gingivitis and periodontal disease: A systematic review. J. Prosthet. Dent. 2023, 130, 816–824. [Google Scholar] [CrossRef]
- Ayash, Y.; Ismailova, A.; Dzhusupov, K.; Chayakova, A.; Aidarkhanova, A. Bridging the implementation gap: Artificial intelligence in periodontology from proof-of-concept to clinical governance—A systematic scoping review with evidence from Kazakhstan. Dent. J. 2026, 14, 615. [Google Scholar] [CrossRef]
- Schwendicke, F.; Samek, W.; Krois, J. Artificial intelligence in dentistry: Chances and challenges. J. Dent. Res. 2020, 99, 769–774. [Google Scholar] [CrossRef]
- Schwendicke, F.; Singh, T.; Lee, J.H.; Gaudin, R.; Chaurasia, A.; Wiegand, T.; Uribe, S.; Krois, J. on behalf of the IADR e-oral health network and the ITU WHO focus group AI for Health Artificial intelligence in dental research: Checklist for authors, reviewers, readers. J. Dent. 2021, 107, 103610. [Google Scholar] [CrossRef]
- Mörch, C.M.; Atsu, S.; Cai, W.; Li, X.; Madathil, S.A.; Liu, X.; Mai, V.; Tamimi, F.; Dilhac, M.A.; Ducret, M. Artificial intelligence and ethics in dentistry: A scoping review. J. Dent. Res. 2021, 100, 1452–1460. [Google Scholar] [CrossRef]
- Rokhshad, R.; Ducret, M.; Chaurasia, A.; Karteva, T.; Radenkovic, M.; Roganovic, J.; Hamdan, M.; Mohammad-Rahimi, H.; Krois, J.; Lahoud, P.; et al. Ethical considerations on artificial intelligence in dentistry: A framework and checklist. J. Dent. 2023, 135, 104593. [Google Scholar] [CrossRef]
- Bitterman, D.S.; Aerts, H.J.W.L.; Mak, R.H. Approaching autonomy in medical artificial intelligence. Lancet Digit. Health 2020, 2, e447–e449. [Google Scholar] [CrossRef]
- Amann, J.; Blasimme, A.; Vayena, E.; Frey, D.; Madai, V.I. on behalf of the Precise4Q consortium Explainability for artificial intelligence in healthcare: A multidisciplinary perspective. BMC Med. Inform. Decis. Mak. 2020, 20, 310. [Google Scholar] [CrossRef]
- Asan, O.; Bayrak, A.E.; Choudhury, A. Artificial intelligence and human trust in healthcare: Focus on clinicians. J. Med. Internet Res. 2020, 22, e15154. [Google Scholar] [CrossRef]
- Lambert, S.I.; Madi, M.; Sopka, S.; Lenes, A.; Stange, H.; Buszello, C.P.; Stephan, A. An integrative review on the acceptance of artificial intelligence among healthcare professionals in hospitals. npj Digit. Med. 2023, 6, 111. [Google Scholar] [CrossRef]
- Price, W.N., II; Gerke, S.; Cohen, I.G. Potential liability for physicians using artificial intelligence. JAMA 2019, 322, 1765–1766. [Google Scholar] [CrossRef]
- Dashti, M.; Londono, J.; Ghasemi, S.; Zare, N.; Samman, M.; Ashi, H.; Amirzade-Iranaq, M.H.; Khosraviani, F.; Sabeti, M.; Khurshid, Z.; et al. Attitudes, knowledge, and perceptions of dentists and dental students toward artificial intelligence: A systematic review. J. Taibah Univ. Med. Sci. 2024, 19, 327–337. [Google Scholar] [CrossRef]
- Hegde, S.; Nanayakkara, S.; Jordan, A.; Zhao, S.; Ang, S.; Bornstein, R.; Zheng, K.; Cao, S.; Zhang, Y.; Sun, J.; et al. Attitudes and perceptions of Australian dentists and dental students towards applications of artificial intelligence in dentistry: A survey. Eur. J. Dent. Educ. 2025, 29, 9–18. [Google Scholar] [CrossRef]
- Kostov, I.I.; Yordanova, G.R. Attitudes of dentists and patients towards the introduction of artificial intelligence in dentistry. J. Med. Life 2025, 18, 472–477. [Google Scholar] [CrossRef]
- Ali, K.; Al-Ali, A.; Safar, M.; Qudeimat, M. Awareness, attitudes, and barriers toward artificial intelligence in dentistry: A cross-sectional survey of dental professionals in Kuwait. Dent. J. 2026, 14, 618. [Google Scholar] [CrossRef]
- Nowakowska, M.; Szalewski, L. Attitudes toward artificial intelligence among Polish dentists: A cross-sectional survey. Diagnostics 2026, 16, 2271. [Google Scholar] [CrossRef]
- Ellakany, P.; Tauqir, S.; Ali, S.; Mikhail, S.S. Artificial intelligence usage among dental students/dentists of different educational level: A multi-country survey. BMC Oral Health 2026, 26, 81. [Google Scholar] [CrossRef]
- Abuel Ela, H.; Moustapha, R.; Badran, A.S.; Abou-Bakr, A.; Almalahy, H.G. Educational gaps and factors associated with artificial intelligence adoption among Egyptian periodontists: A multicenter cross-sectional study. Sci. Rep. 2026, 16. [Google Scholar] [CrossRef]
- Chawla, R.L.; Gadge, N.P.; Ronad, S.; Waghmare, A.; Patil, A.; Deshmukh, G. Knowledge, attitude and perception regarding artificial intelligence in periodontology: A questionnaire study. Cureus 2023, 15, e48309. [Google Scholar] [CrossRef]
- Bharathi, S.H.; Ismail, B.M.; Kumar, K.H.; Sadananda, K.; Radhika, B.; Halemani, S. Assessment of dentists’ knowledge, attitude and practice regarding artificial intelligence in periodontics. Bioinformation 2026, 22, 2712–2717. [Google Scholar] [CrossRef]
- Mihut, T.; Pantea, M.; Chivu, R.D.; Popescu-Spineni, D.; Cristache, C.M. Responsible clinical AI in dentistry: Trust, professional autonomy, and perceptions of accountability across stakeholders in Romania—A multidisciplinary cross-sectional survey. Healthcare 2026, 14, 3003. [Google Scholar] [CrossRef]
- Kosan, E.; Krois, J.; Wingenfeld, K.; Deuter, C.E.; Gaudin, R.; Schwendicke, F. Patients’ perspectives on artificial intelligence in dentistry: A controlled study. J. Clin. Med. 2022, 11, 2143. [Google Scholar] [CrossRef]
- Republic of Kazakhstan. Law of the Republic of Kazakhstan No. 230-VIII of 17 November 2025 “On Artificial Intelligence”. Astana, Kazakhstan, 2025. Available online: https://adilet.zan.kz/ (accessed on 29 September 2026).
- Library of Congress. Kazakhstan: New Law Introduces Rules for AI Systems Operating in the Country. Global Legal Monitor, 12 January 2026. Available online: https://www.loc.gov/item/global-legal-monitor/2026-01-12/kazakhstan-new-law-introduces-rules-for-ai-systems-operating-in-the-country (accessed on 29 September 2026).
- European Parliament; Council of the European Union. Regulation (EU) 2024/1689 of 13 June 2024 laying down harmonised rules on artificial intelligence (Artificial Intelligence Act); Off. J. Eur. Union 2024, L, 12 July 2024, 2024. Available online: http://data.europa.eu/eli/reg/2024/1689/oj (accessed on 29 September 2026).
- World Health Organization. Ethics and Governance of Artificial Intelligence for Health: WHO Guidance; World Health Organization: Geneva, Switzerland, 2021; Available online: https://www.who.int/publications/i/item/9789240029200 (accessed on 29 September 2026).
- Sharma, A.; Minh Duc, N.T.; Luu Lam Thang, T.; Nam, N.H.; Ng, S.J.; Abbas, K.S.; Huy, N.T.; Marušić, A.; Paul, C.L.; Kwok, J.; et al. A Consensus-Based Checklist for Reporting of Survey Studies (CROSS). J. Gen. Intern. Med. 2021, 36, 3179–3187. [Google Scholar] [CrossRef]
- Eysenbach, G. Improving the quality of web surveys: The Checklist for Reporting Results of Internet E-Surveys (CHERRIES). J. Med. Internet Res. 2004, 6, e34. [Google Scholar] [CrossRef]
- von Elm, E.; Altman, D.G.; Egger, M.; Pocock, S.J.; Gøtzsche, P.C.; Vandenbroucke, J.P. STROBE Initiative The Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement: Guidelines for reporting observational studies. Lancet 2007, 370, 1453–1457. [Google Scholar] [CrossRef]
- Eke, P.I.; Dye, B.A.; Wei, L.; Slade, G.D.; Thornton-Evans, G.O.; Beck, J.D.; Taylor, G.W.; Borgnakke, W.S.; Page, R.C.; Genco, R.J. Self-reported measures for surveillance of periodontitis. J. Dent. Res. 2013, 92, 1041–1047. [Google Scholar] [CrossRef]
- Peduzzi, P.; Concato, J.; Kemper, E.; Holford, T.R.; Feinstein, A.R. A simulation study of the number of events per variable in logistic regression analysis. J. Clin. Epidemiol. 1996, 49, 1373–1379. [Google Scholar] [CrossRef]
- Newcombe, R.G. Two-sided confidence intervals for the single proportion: Comparison of seven methods. Stat. Med. 1998, 17, 857–872. [Google Scholar] [CrossRef]
- Verhulst, M.J.L.; Teeuw, W.J.; Bizzarro, S.; Muris, J.; Su, N.; Nicu, E.A.; Nazmi, K.; Bikker, F.J.; Loos, B.G. A rapid, non-invasive tool for periodontitis screening in a medical care setting. BMC Oral Health 2019, 19, 87. [Google Scholar] [CrossRef]
- Genco, R.J.; Borgnakke, W.S. Diabetes as a potential risk for periodontitis: Association studies. Periodontol. 2000 2020, 83, 40–45. [Google Scholar] [CrossRef]
- Coelho, J.M.F.; Miranda, S.S.; da Cruz, S.S.; Trindade, S.C.; Passos-Soares, J.S.; Cerqueira, E.M.M.; Costa, M.C.N.; Figueiredo, A.C.M.G.; Hintz, A.M.; Barreto, M.L.; et al. Is there association between stress and periodontitis? Clin. Oral Investig. 2020, 24, 2285–2294. [Google Scholar] [CrossRef]
- Decker, A.M.; Kapila, Y.L.; Wang, H.L. The psychobiological links between chronic stress-related diseases, periodontal/peri-implant diseases, and wound healing. Periodontol. 2000 2021, 87, 94–106. [Google Scholar] [CrossRef]
- Nibali, L.; Bayliss-Chapman, J.; Almofareh, S.A.; Zhou, Y.; Divaris, K.; Vieira, A.R. What is the heritability of periodontitis? A systematic review. J. Dent. Res. 2019, 98, 632–641. [Google Scholar] [CrossRef]
- Leite, F.R.M.; Nascimento, G.G.; Scheutz, F.; López, R. Effect of smoking on periodontitis: A systematic review and meta-regression. Am. J. Prev. Med. 2018, 54, 831–841. [Google Scholar] [CrossRef]
- Chayakova, A.; Tsigengagel, O.; Zhussupova, G. Beyond clinical acuity: Cardiac comorbidity and complication profiles and the prehospital hospitalization/transport decision in ischemic heart disease—A five-year retrospective emergency medical service study in Astana, Kazakhstan. Healthcare 2026, 14, 2308. [Google Scholar] [CrossRef]
Figure 1.
Data-processing flowchart from the raw questionnaire exports to the analytical samples for the three surveys. PHC, primary health care; α, Cronbach’s alpha.
Figure 1.
Data-processing flowchart from the raw questionnaire exports to the analytical samples for the three surveys. PHC, primary health care; α, Cronbach’s alpha.
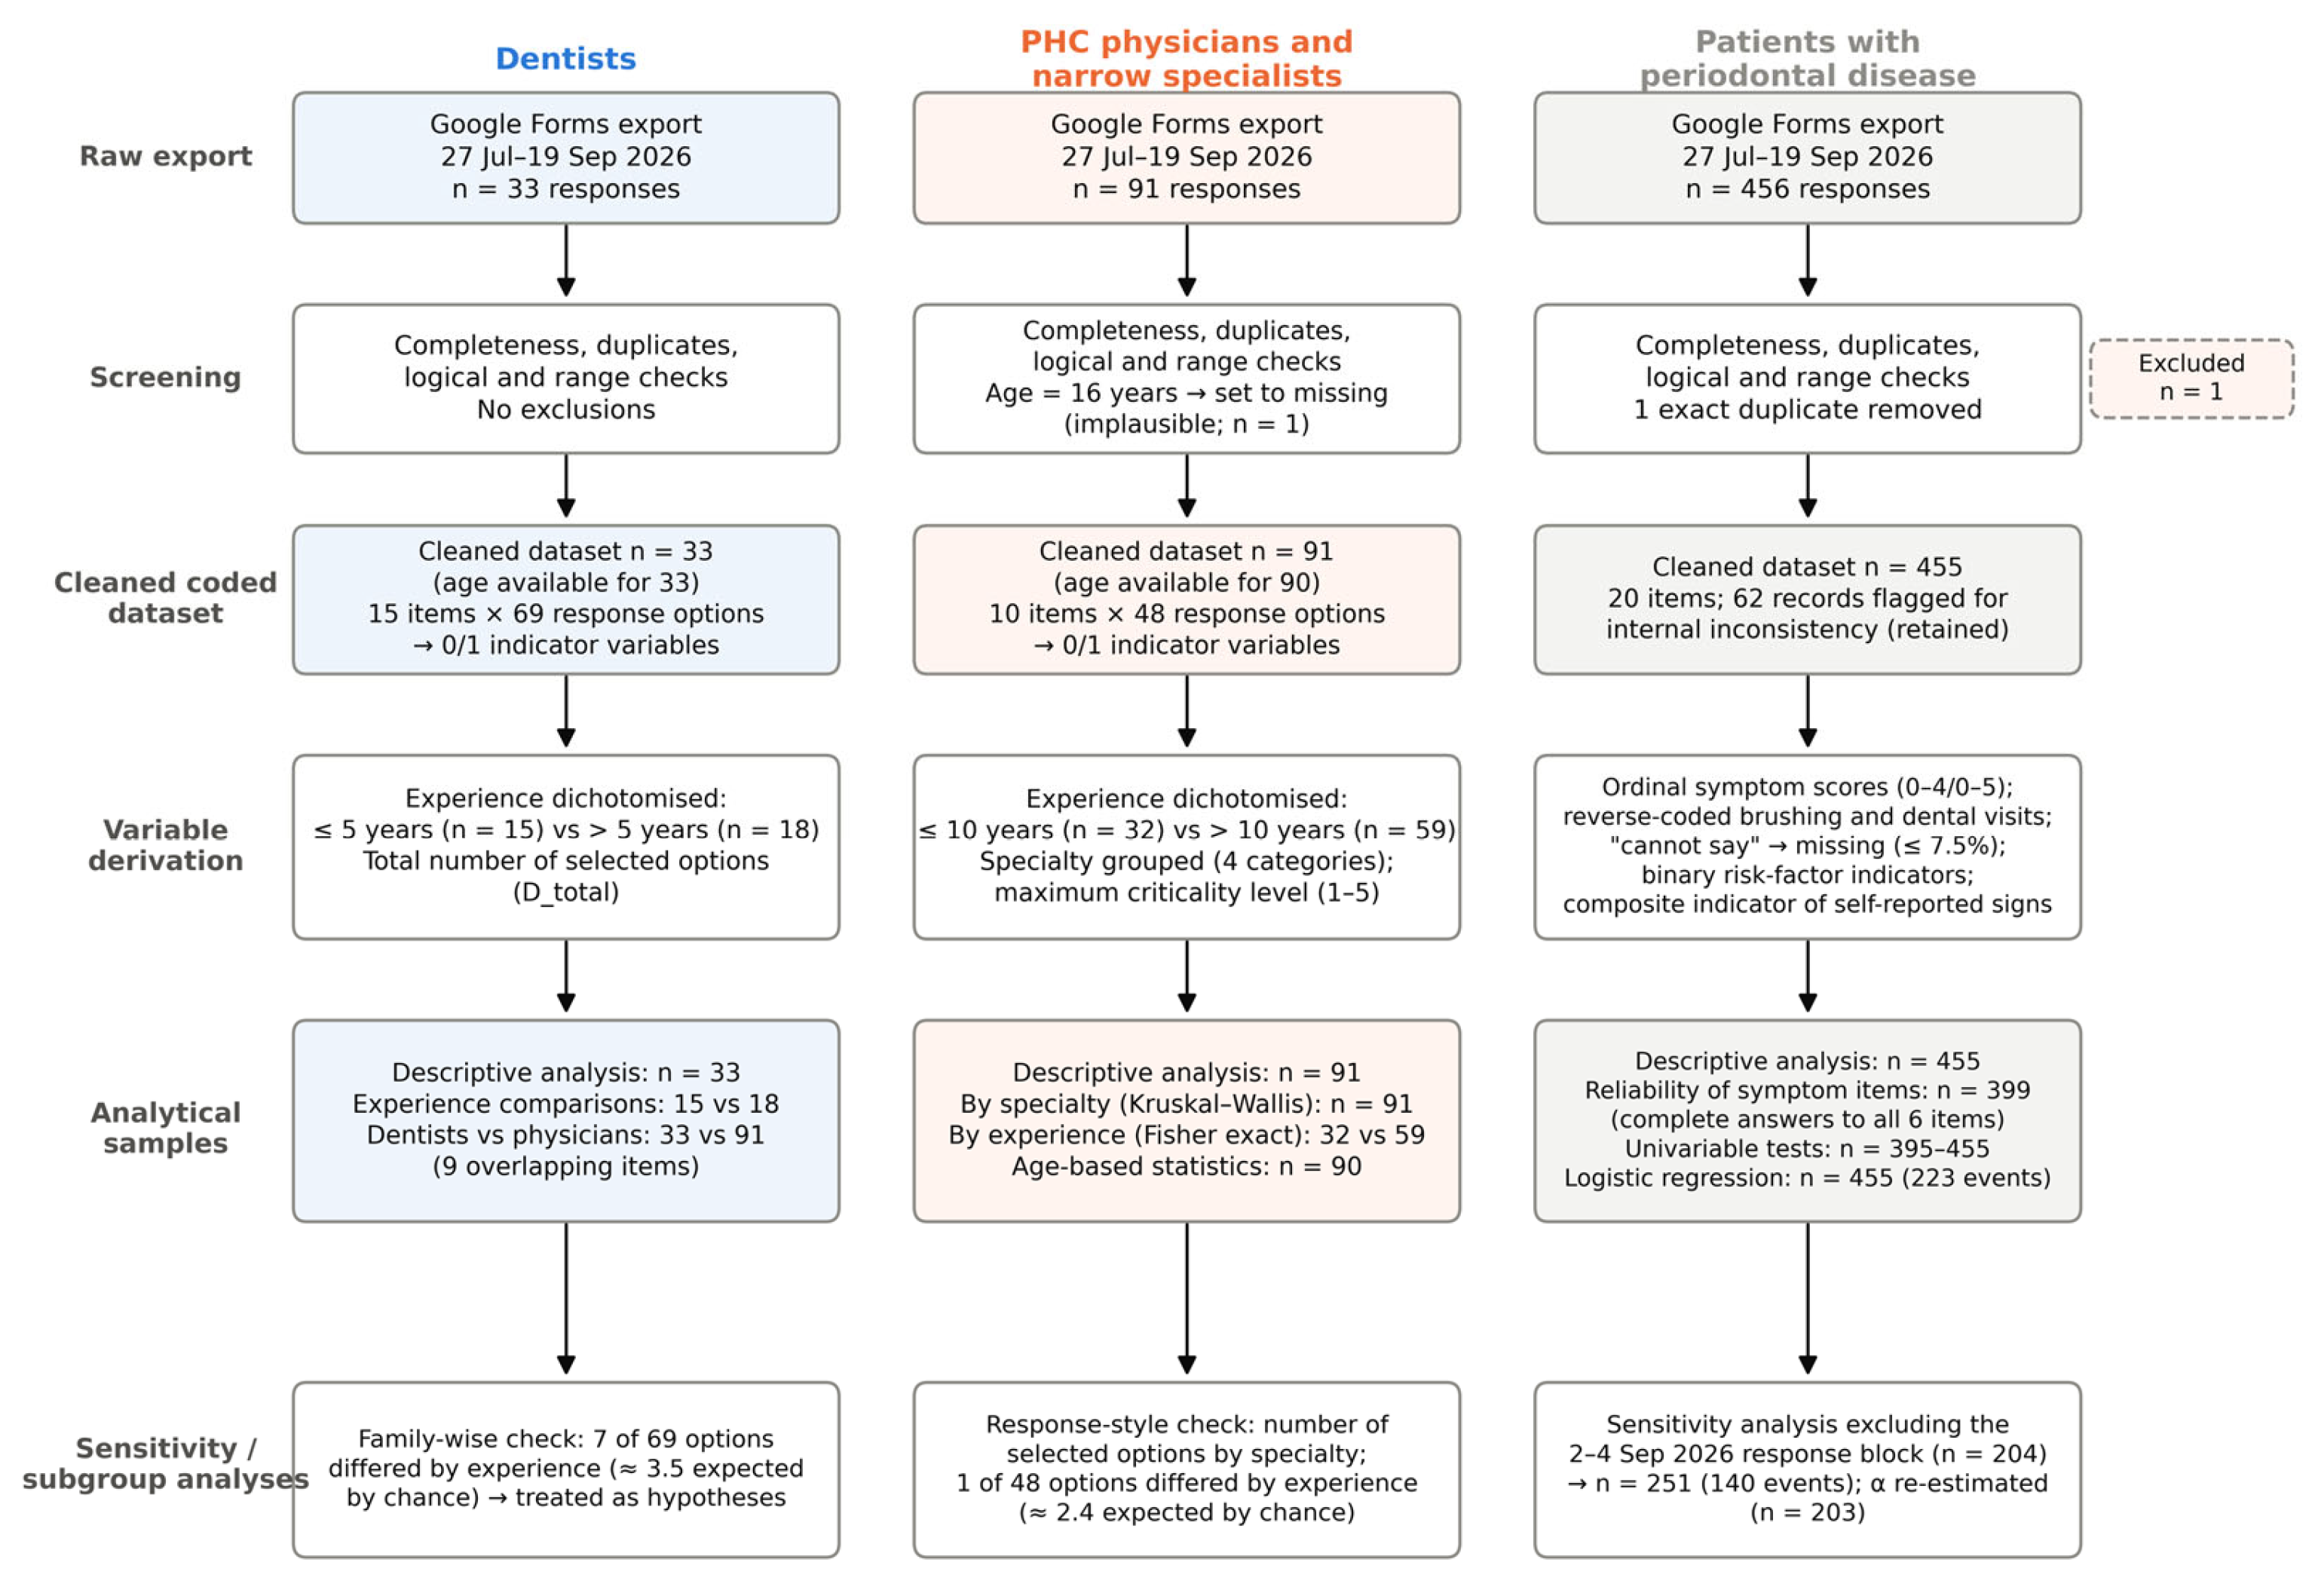
Figure 2.
Dentists’ views on integration of AI (n = 33): (a) perceived barriers to AI integration into daily practice (percentage of respondents with 95% Wilson confidence intervals); (b) acceptable level of AI autonomy according to professional experience (percentage within each experience group). CDSS, clinical decision-support system.
Figure 2.
Dentists’ views on integration of AI (n = 33): (a) perceived barriers to AI integration into daily practice (percentage of respondents with 95% Wilson confidence intervals); (b) acceptable level of AI autonomy according to professional experience (percentage within each experience group). CDSS, clinical decision-support system.
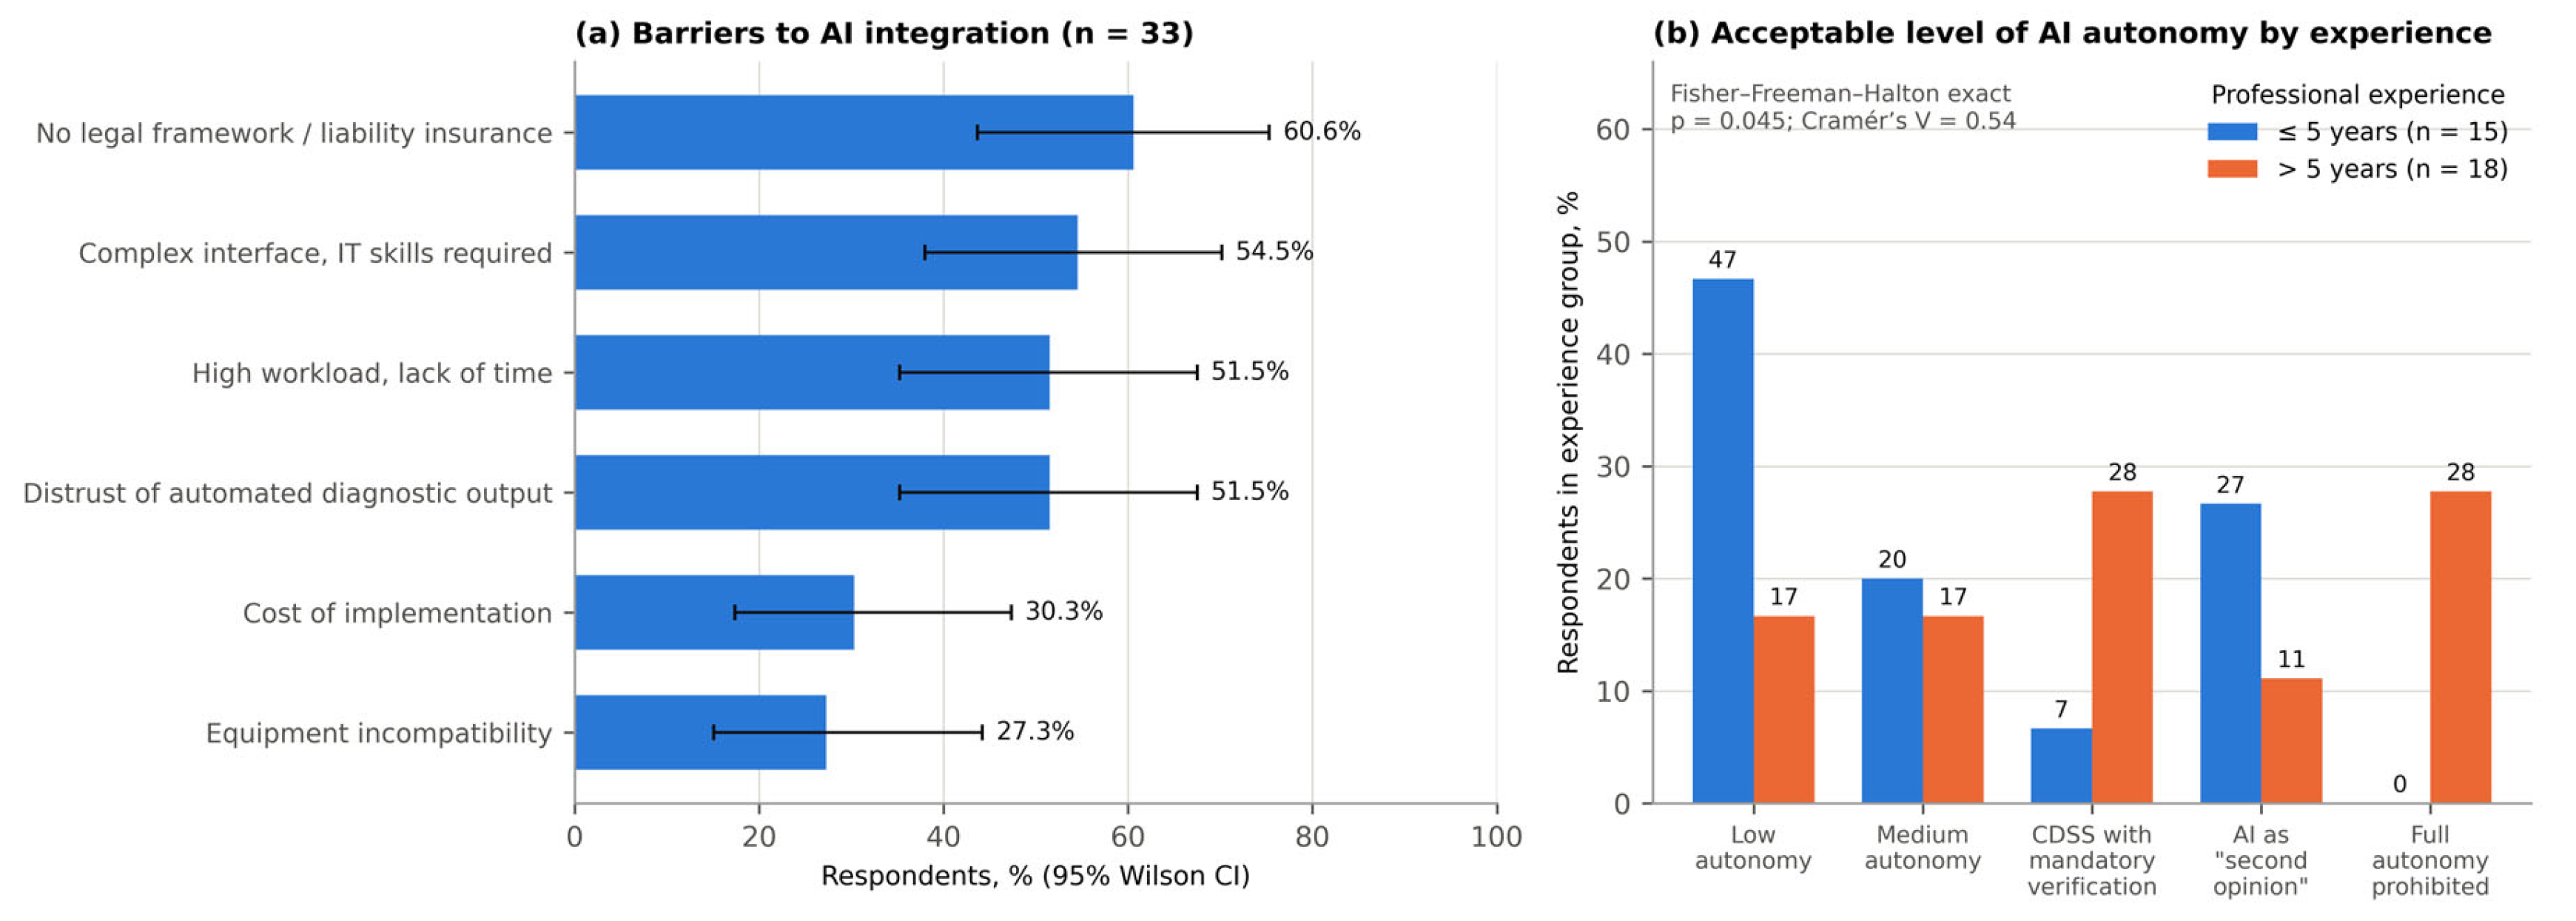
Figure 3.
Views of primary health care (PHC) physicians and medical specialists (n = 91): (a) barriers to oral examination during a medical consultation; (b) stage at which PHC involvement in periodontal care is considered most effective; (c) priority groups for AI-assisted periodontal screening. Bars show the percentage of respondents with 95% Wilson confidence intervals.
Figure 3.
Views of primary health care (PHC) physicians and medical specialists (n = 91): (a) barriers to oral examination during a medical consultation; (b) stage at which PHC involvement in periodontal care is considered most effective; (c) priority groups for AI-assisted periodontal screening. Bars show the percentage of respondents with 95% Wilson confidence intervals.
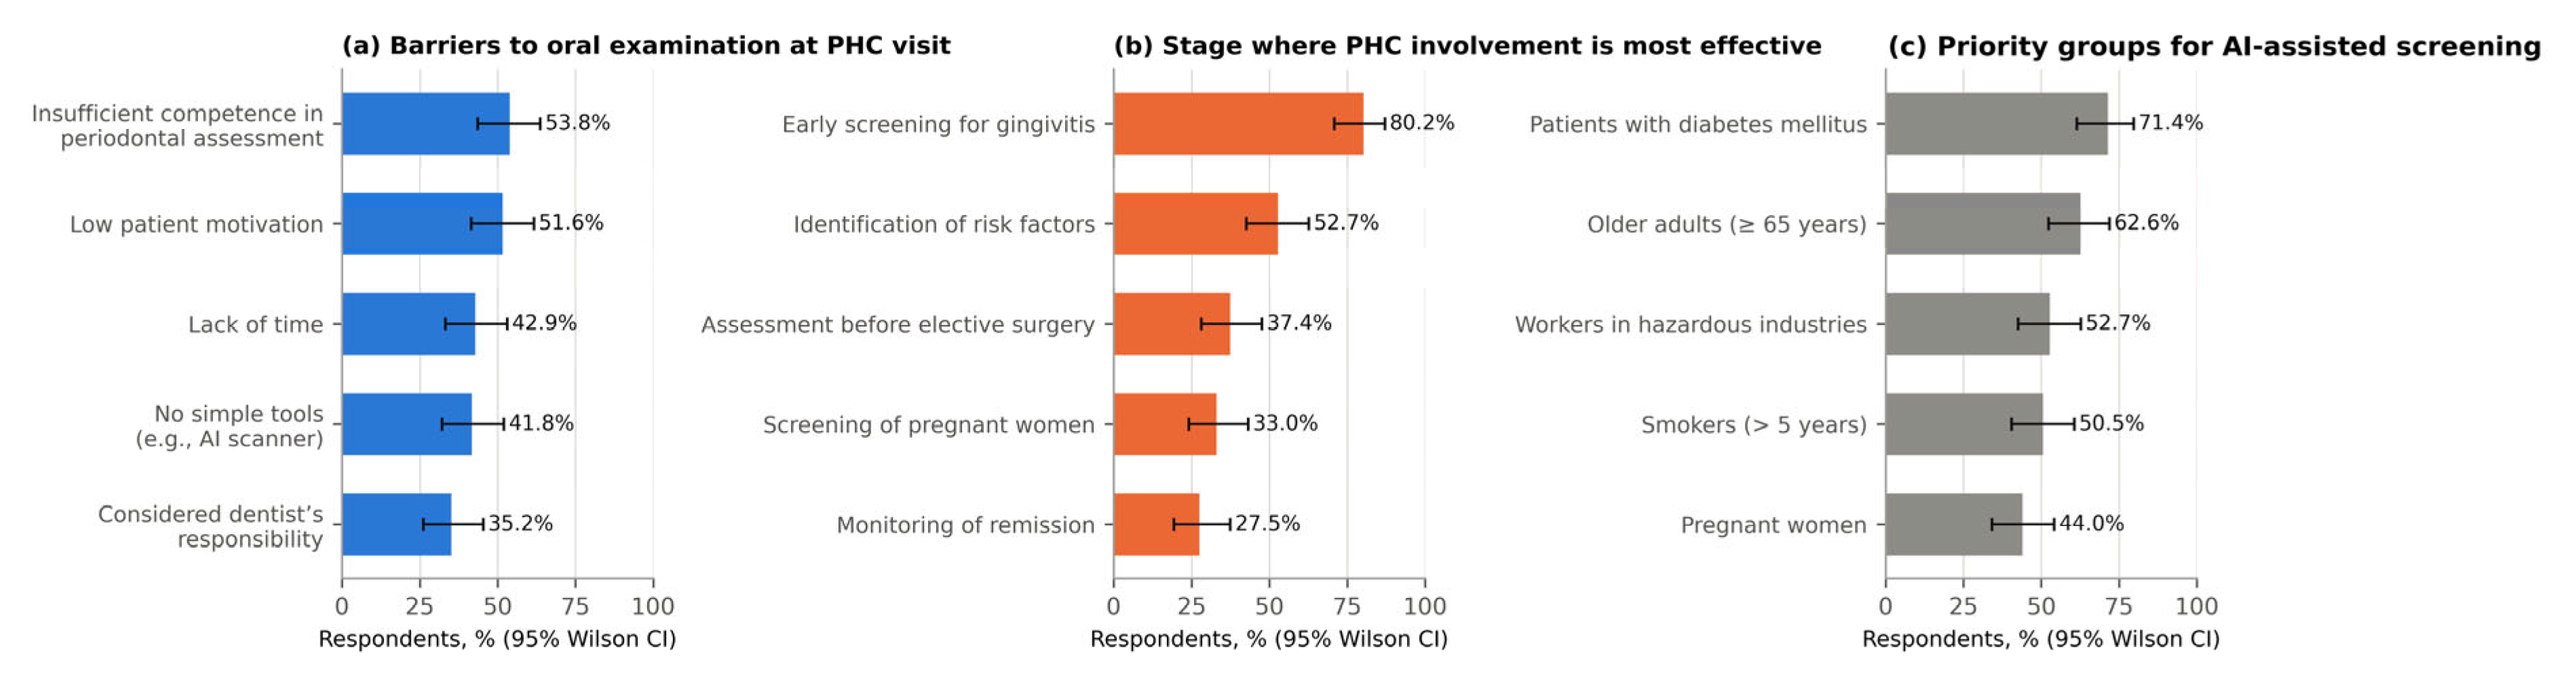
Figure 4.
Comorbid conditions that an AI algorithm should take into account: comparison of dentists (n = 33) and PHC physicians/specialists (n = 91). Points show the percentage of respondents selecting each condition.
Figure 4.
Comorbid conditions that an AI algorithm should take into account: comparison of dentists (n = 33) and PHC physicians/specialists (n = 91). Points show the percentage of respondents selecting each condition.
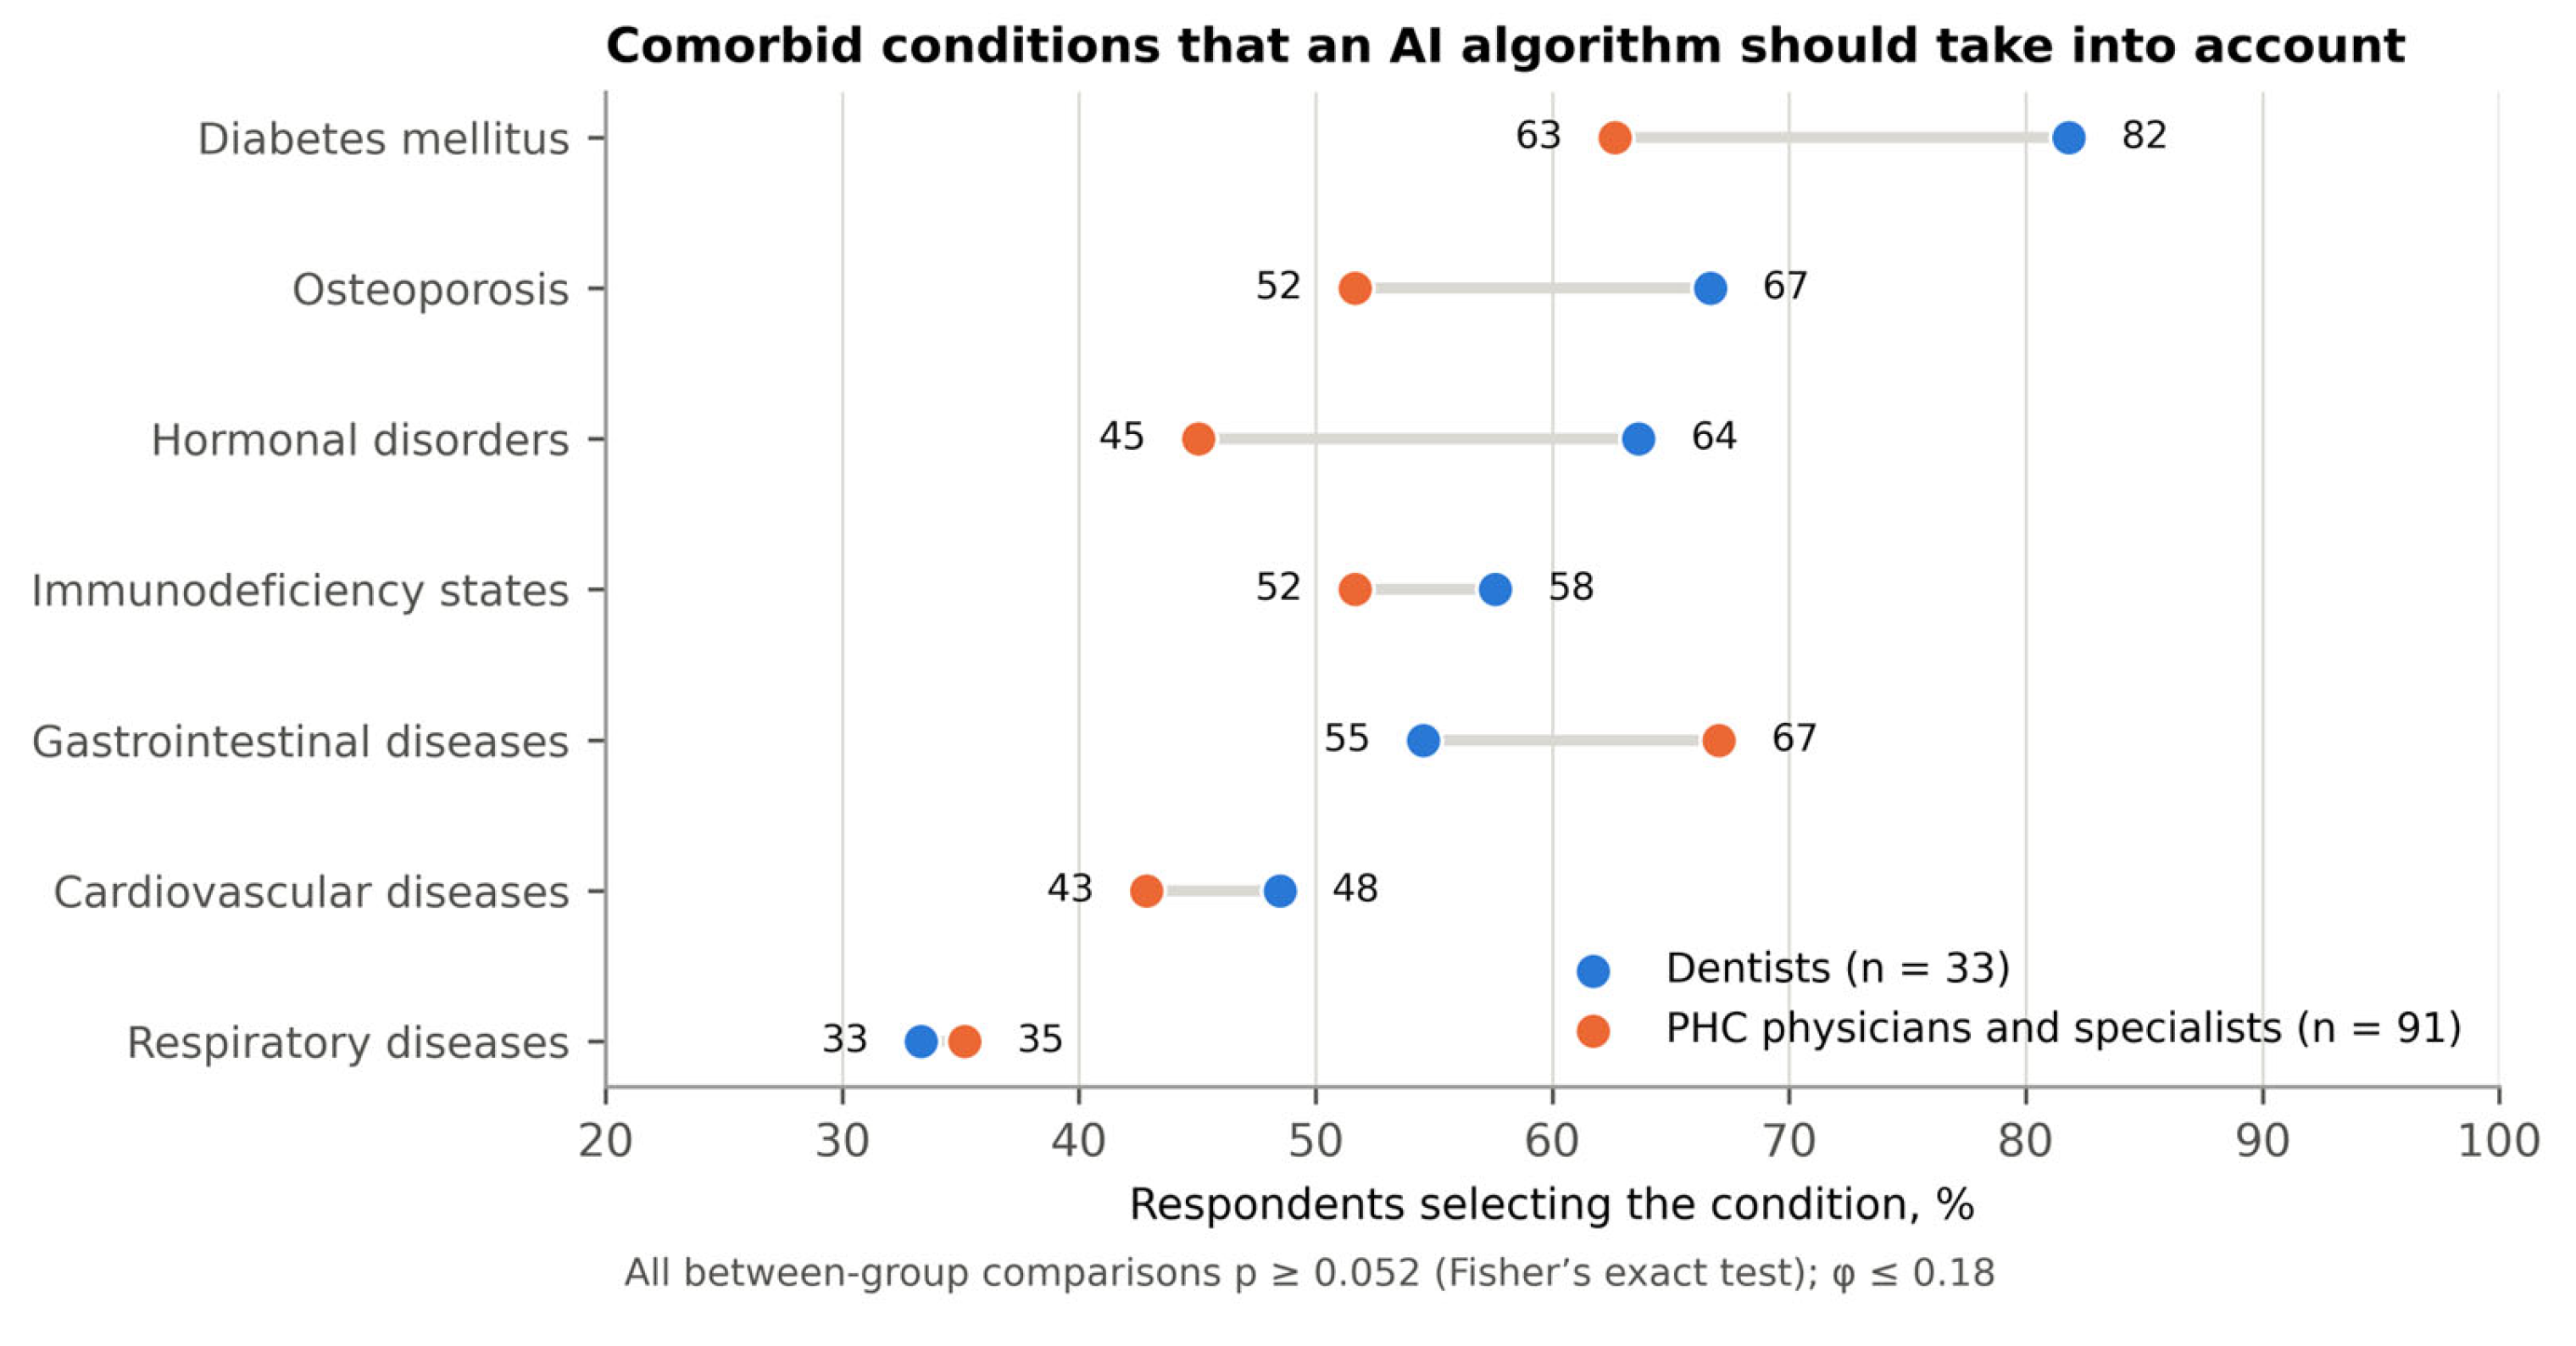
Figure 5.
Self-reported signs of periodontal disease in patients (n = 455): (a) proportion of patients with signs by age group (95% Wilson confidence intervals; dashed line, overall proportion); (b) adjusted odds ratios (aOR) with 95% confidence intervals from the multivariable logistic regression (orange, confidence interval excluding 1).
Figure 5.
Self-reported signs of periodontal disease in patients (n = 455): (a) proportion of patients with signs by age group (95% Wilson confidence intervals; dashed line, overall proportion); (b) adjusted odds ratios (aOR) with 95% confidence intervals from the multivariable logistic regression (orange, confidence interval excluding 1).
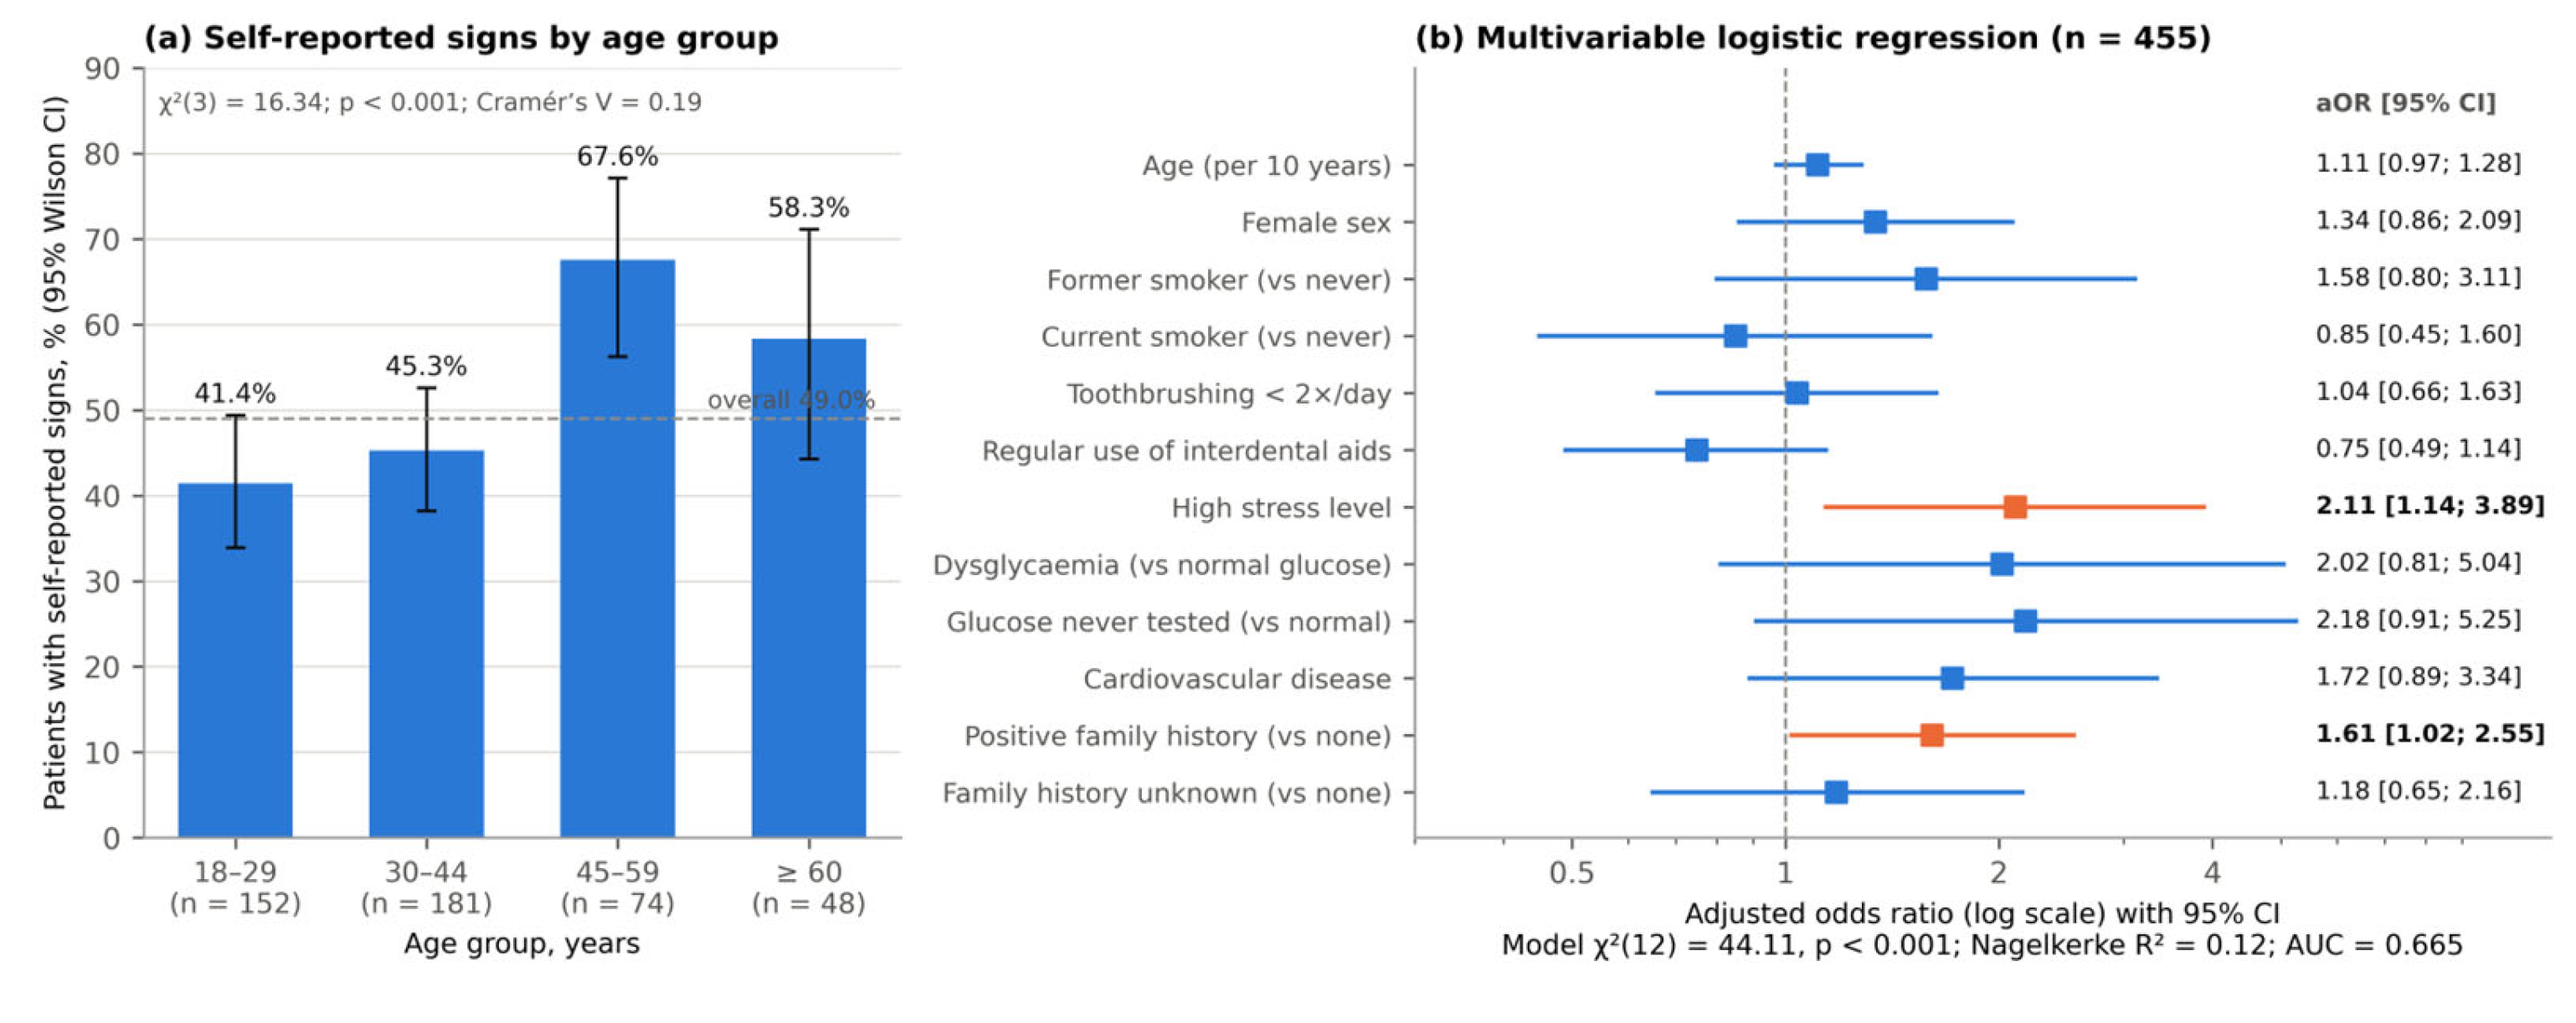

Table 1.
Characteristics of the study participants.
| Characteristic | Dentists (n = 33) | PHC physicians and specialists (n = 91) | Patients (n = 455) |
|---|---|---|---|
| Age, years: Me [Q1; Q3] | 33 [24; 40] | 42 [35; 55.8] ¹ | 40 [22; 47] |
| Age, years: min–max | 23–53 | 22–70 | 18–77 |
| Men, n (%) | 21 (63.6) | 12 (13.2) | 148 (32.5) |
| Women, n (%) | 12 (36.4) | 79 (86.8) | 307 (67.5) |
| Residence/work in Astana, n (%) | 28 (84.8) | 28 (30.8) | 288 (63.3) |
| Polyclinic, n (%) | 2 (6.1) | 66 (72.5) | – |
| Hospital, n (%) | 2 (6.1) | 11 (12.1) | – |
| Private clinic, n (%) | 29 (87.9) | 13 (14.3) | – |
| Professional experience < 1 year, n (%) | 3 (9.1) | 5 (5.5) | – |
| Professional experience 1–5 years, n (%) | 12 (36.4) | 9 (9.9) | – |
| Professional experience 5–10 years, n (%) | 3 (9.1) | 18 (19.8) | – |
| Professional experience 10–15 years, n (%) | 5 (15.2) | 19 (20.9) | – |
| Professional experience > 15 years, n (%) | 10 (30.3) | 40 (44.0) | – |
| Age 18–29 years, n (%) | – | – | 152 (33.4) |
| Age 30–44 years, n (%) | – | – | 181 (39.8) |
| Age 45–59 years, n (%) | – | – | 74 (16.3) |
| Age ≥ 60 years, n (%) | – | – | 48 (10.5) |
| On dispensary register, n (%) | – | – | 42 (9.2) |
¹ n = 90 (one implausible value set to missing). Me, median; Q1, Q3, first and third quartiles; PHC, primary health care.
Table 2.
Most frequent responses of dentists (n = 33) to the multiple-choice items on the requirements for an AI-enabled periodontal decision-support system.
Table 2.
Most frequent responses of dentists (n = 33) to the multiple-choice items on the requirements for an AI-enabled periodontal decision-support system.
| Item | Three most frequent options: n (%) [95% CI, %] |
|---|---|
| Q1. Examination procedures to automate first | History-taking and complaints, 27 (81.8) [65.6–91.4]; visual assessment of the gingiva, 24 (72.7) [55.8–84.9]; probing of pocket depth, 21 (63.6) [46.6–77.8] |
| Q2. Radiographic signs on panoramic radiographs | Destruction of the cortical plate of the interdental septa, 30 (90.9) [76.4–96.9]; widening of the periodontal ligament space, 25 (75.8) [59.0–87.2]; depth of bony pockets, 22 (66.7) [49.6–80.2] |
| Q3. Comorbid conditions for the AI algorithm | Diabetes mellitus, 27 (81.8) [65.6–91.4]; osteoporosis, 22 (66.7) [49.6–80.2]; hormonal disorders, 21 (63.6) [46.6–77.8] |
| Q4. Indices difficult to compute without digital assistance | PMA index, 20 (60.6) [43.7–75.3]; Greene–Vermillion index, 19 (57.6) [40.8–72.8]; CPITN, 16 (48.5) [32.5–64.8] |
| Q5. Risk factors for the prevention plan | Quality of oral hygiene, 28 (84.8) [69.1–93.3]; smoking duration, 24 (72.7) [55.8–84.9]; malocclusion, 24 (72.7) [55.8–84.9] |
| Q6. Stage at which AI is most needed | Early diagnosis of gingivitis, 23 (69.7) [52.7–82.6]; differential diagnosis of mild vs. moderate periodontitis, 20 (60.6) [43.7–75.3]; screening of healthy individuals, 19 (57.6) [40.8–72.8] |
| Q7. Acceptable level of AI autonomy (single choice) | Low autonomy (AI processes data only), 10 (30.3) [17.4–47.3]; medium autonomy, 6 (18.2) [8.6–34.4]; decision support with mandatory verification, 6 (18.2) [8.6–34.4] |
| Q8. Laboratory data to be matched | Glucose > 6 mmol/L, 23 (69.7) [52.7–82.6]; leukocytes, 22 (66.7) [49.6–80.2]; cytokines (IL-8, IL-2), 22 (66.7) [49.6–80.2] |
| Q9. Priority AI function | Remote monitoring, 22 (66.7) [49.6–80.2]; index calculation from photographs, 20 (60.6) [43.7–75.3]; predictive analysis of tooth loss, 19 (57.6) [40.8–72.8] |
| Q10. Anatomical risk factors | Tooth crowding, 24 (72.7) [55.8–84.9]; mucosal cords, 21 (63.6) [46.6–77.8]; abnormal frenula, 21 (63.6) [46.6–77.8] |
| Q11. Frequency of risk re-assessment | Four times a year, 24 (72.7) [55.8–84.9]; twice a year, 18 (54.5) [38.0–70.2]; monthly, 14 (42.4) [27.2–59.2] |
| Q12. Preferred output format | Graphical periodontal chart, 22 (66.7) [49.6–80.2]; text with ICD-10 code, 19 (57.6) [40.8–72.8]; probabilistic prognosis (%), 18 (54.5) [38.0–70.2] |
| Q13. Most important aspect of transparency (single choice) | Access to source data, 12 (36.4) [22.2–53.4]; delimitation of responsibility, 10 (30.3) [17.4–47.3]; explanation of the reasoning, 7 (21.2) [10.7–37.8] |
| Q14. Criteria of treatment success | Reduction in probing depth, 25 (75.8) [59.0–87.2]; stabilisation of septal height, 23 (69.7) [52.7–82.6]; reduced mobility, 19 (57.6) [40.8–72.8] |
| Q15. Barriers to AI integration | No legal framework/liability insurance, 20 (60.6) [43.7–75.3]; complex interface and IT skills, 18 (54.5) [38.0–70.2]; workload and lack of time, 17 (51.5) [35.2–67.5] |
Percentages are calculated from the number of respondents and may sum to more than 100% within an item. CI, Wilson confidence interval; PMA, papillary–marginal–alveolar index; CPITN, Community Periodontal Index of Treatment Needs.
Table 3.
Acceptable level of AI autonomy and priority aspect of transparency according to dentists’ professional experience, n (%).
Table 3.
Acceptable level of AI autonomy and priority aspect of transparency according to dentists’ professional experience, n (%).
| Response option | ≤ 5 years (n = 15) | > 5 years (n = 18) |
|---|---|---|
| Q7. Low autonomy (AI processes data only) | 7 (46.7) | 3 (16.7) |
| Q7. Medium autonomy | 3 (20.0) | 3 (16.7) |
| Q7. Decision support with mandatory verification | 1 (6.7) | 5 (27.8) |
| Q7. AI as a “second opinion” | 4 (26.7) | 2 (11.1) |
| Q7. Full autonomy prohibited | 0 (0.0) | 5 (27.8) |
| Q7: χ²(4) = 9.74, p = 0.045; exact p = 0.045; Cramér’s V = 0.54 | ||
| Q13. Access to source data | 8 (53.3) | 4 (22.2) |
| Q13. Explanation of the reasoning | 4 (26.7) | 3 (16.7) |
| Q13. Operational limitations | 2 (13.3) | 0 (0.0) |
| Q13. Labelling of synthetic results | 0 (0.0) | 2 (11.1) |
| Q13. Delimitation of responsibility | 1 (6.7) | 9 (50.0) |
| Q13: χ²(4) = 11.70, p = 0.020; exact p = 0.012; Cramér’s V = 0.60 | ||
Pearson’s χ² and Fisher–Freeman–Halton exact test for 2 × 5 tables. Expected frequencies were below 5 in 9 of 10 cells for Q7 (minimum 2.27) and 7 of 10 cells for Q13 (minimum 0.91); inference is based on the exact p value.
Table 4.
Most frequent responses of PHC physicians and medical specialists (n = 91).
| Item | Three most frequent options: n (%) [95% CI, %] |
|---|---|
| Q4. Importance of periodontal status for diabetes compensation | Important (indicator of angiopathy), 46 (50.5) [40.5–60.6]; very important, 45 (49.5) [39.4–59.5]; extremely critical, 42 (46.2) [36.3–56.3] |
| Q5. Anamnestic factors of severe periodontitis | Duration of the systemic disease, 69 (75.8) [66.1–83.5]; smoking duration, 61 (67.0) [56.9–75.8]; heredity, 40 (44.0) [34.2–54.2] |
| Q6. Comorbidities for automatic AI alerts | Gastrointestinal diseases, 61 (67.0) [56.9–75.8]; diabetes mellitus, 57 (62.6) [52.4–71.9]; osteoporosis, 47 (51.6) [41.5–61.6] |
| Q7. Complete blood count findings warranting referral to a periodontist | Leukocytosis/leukopenia, 53 (58.2) [48.0–67.8]; raised ESR without a focus, 52 (57.1) [46.9–66.8]; aplastic anaemia/agranulocytosis, 47 (51.6) [41.5–61.6] |
| Q8. Complaints indicating gingivitis | Gingival bleeding, 70 (76.9) [67.3–84.4]; periodic swelling, 58 (63.7) [53.5–72.9]; halitosis, 53 (58.2) [48.0–67.8] |
| Q9. Barriers to oral examination by a PHC physician | Insufficient competence, 49 (53.8) [43.7–63.7]; low patient motivation, 47 (51.6) [41.5–61.6]; lack of time, 39 (42.9) [33.2–53.1] |
| Q10. Best indicator of quality-of-life impact (single choice) | Emergency visits, 30 (33.0) [24.2–43.1]; economic costs, 22 (24.2) [16.5–33.9]; restrictions in food choice, 19 (20.9) [13.8–30.3] |
| Q11. Stage at which PHC involvement is most effective | Early screening for gingivitis, 73 (80.2) [70.9–87.1]; identification of risk factors, 48 (52.7) [42.6–62.7]; assessment before elective surgery, 34 (37.4) [28.1–47.6] |
| Q12. Periodontal changes in gastrointestinal disease | Catarrhal/ulcerative processes, 64 (70.3) [60.3–78.7]; persistent plaque, 50 (54.9) [44.7–64.8]; recurrent course, 49 (53.8) [43.7–63.7] |
| Q13. Priority groups for AI-assisted screening | Patients with diabetes, 65 (71.4) [61.4–79.7]; adults ≥ 65 years, 57 (62.6) [52.4–71.9]; workers in hazardous industries, 48 (52.7) [42.6–62.7] |
Percentages are calculated from the number of respondents and may sum to more than 100% within an item. CI, Wilson confidence interval; ESR, erythrocyte sedimentation rate; PHC, primary health care.
Table 5.
Comparison of dentists and PHC physicians/specialists on overlapping questionnaire items.
| Item | Dentists (n = 33), n (%) | Physicians (n = 91), n (%) | OR [95% CI] | p | φ |
|---|---|---|---|---|---|
| Diabetes mellitus | 27 (81.8) | 57 (62.6) | 2.68 [1.01; 7.16] | 0.052 | 0.18 |
| Gastrointestinal diseases | 18 (54.5) | 61 (67.0) | 0.59 [0.26; 1.33] | 0.212 | 0.11 |
| Cardiovascular diseases | 16 (48.5) | 39 (42.9) | 1.25 [0.56; 2.79] | 0.683 | 0.05 |
| Respiratory diseases | 11 (33.3) | 32 (35.2) | 0.92 [0.40; 2.14] | 1.000 | 0.02 |
| Hormonal disorders | 21 (63.6) | 41 (45.1) | 2.13 [0.94; 4.85] | 0.103 | 0.16 |
| Osteoporosis | 22 (66.7) | 47 (51.6) | 1.87 [0.81; 4.30] | 0.156 | 0.13 |
| Immunodeficiency states | 19 (57.6) | 47 (51.6) | 1.27 [0.57; 2.84] | 0.684 | 0.05 |
| Stage: early diagnosis/screening of gingivitis | 23 (69.7) | 73 (80.2) | 0.57 [0.23; 1.40] | 0.231 | 0.11 |
| Stage: monitoring of remission | 18 (54.5) | 25 (27.5) | 3.17 [1.39; 7.23] | 0.010 | 0.25 |
Fisher’s exact test (two-sided). OR, odds of selection by dentists relative to physicians, with Woolf 95% CI. The first seven rows refer to comorbid conditions to be considered by the AI algorithm.
Table 6.
Frequency of self-reported signs of periodontal disease according to risk factors (patients, n = 455).
Table 6.
Frequency of self-reported signs of periodontal disease according to risk factors (patients, n = 455).
| Factor | Factor present: n/N (%) | Factor absent: n/N (%) | OR [95% CI] | χ²(1) | p | φ |
|---|---|---|---|---|---|---|
| Female sex | 159/307 (51.8) | 64/148 (43.2) | 1.41 [0.95; 2.09] | 2.92 | 0.087 | 0.08 |
| Current smoking | 30/58 (51.7) | 193/397 (48.6) | 1.13 [0.65; 1.97] | 0.20 | 0.658 | 0.02 |
| Toothbrushing < 2 times/day | 71/137 (51.8) | 152/318 (47.8) | 1.17 [0.79; 1.75] | 0.62 | 0.431 | 0.04 |
| High stress level | 43/62 (69.4) | 180/393 (45.8) | 2.68 [1.51; 4.76] | 11.89 | < 0.001 | 0.16 |
| Dysglycaemia ¹ | 24/32 (75.0) | 183/398 (46.0) | 3.52 [1.55; 8.04] | 9.99 | 0.002 | 0.15 |
| Cardiovascular disease | 45/64 (70.3) | 178/391 (45.5) | 2.83 [1.60; 5.02] | 13.52 | < 0.001 | 0.17 |
| Positive family history ¹ | 79/129 (61.2) | 112/266 (42.1) | 2.17 [1.41; 3.34] | 12.74 | < 0.001 | 0.18 |
| Dental visits ≥ once a year | 117/244 (48.0) | 106/211 (50.2) | 0.91 [0.63; 1.32] | 0.24 | 0.627 | 0.02 |
Pearson’s χ² test (all expected frequencies ≥ 5); OR with Woolf 95% CI. ¹ Patients who had never had their glucose measured (n = 25) or who did not know their family history (n = 60) were excluded from the respective comparison.
Table 7.
Multivariable binary logistic regression: factors associated with self-reported signs of periodontal disease (patients, n = 455; 223 events).
Table 7.
Multivariable binary logistic regression: factors associated with self-reported signs of periodontal disease (patients, n = 455; 223 events).
| Predictor | B | SE | Wald χ² | p | Adjusted OR [95% CI] | VIF |
|---|---|---|---|---|---|---|
| Constant | −0.927 | 0.374 | 6.13 | 0.013 | 0.40 [0.19; 0.82] | – |
| Age (per 10 years) | 0.108 | 0.073 | 2.23 | 0.135 | 1.11 [0.97; 1.28] | 1.21 |
| Female sex | 0.294 | 0.225 | 1.71 | 0.192 | 1.34 [0.86; 2.09] | 1.14 |
| Former smoker (vs. never) | 0.456 | 0.346 | 1.73 | 0.188 | 1.58 [0.80; 3.11] | 1.12 |
| Current smoker (vs. never) | −0.163 | 0.324 | 0.25 | 0.616 | 0.85 [0.45; 1.60] | 1.19 |
| Toothbrushing < 2 times/day | 0.039 | 0.230 | 0.03 | 0.864 | 1.04 [0.66; 1.63] | 1.14 |
| Regular use of interdental aids | −0.293 | 0.216 | 1.83 | 0.176 | 0.75 [0.49; 1.14] | 1.15 |
| High stress level | 0.746 | 0.313 | 5.69 | 0.017 | 2.11 [1.14; 3.89] | 1.09 |
| Dysglycaemia (vs. normal glucose) | 0.705 | 0.465 | 2.30 | 0.130 | 2.02 [0.81; 5.04] | 1.24 |
| Glucose never tested (vs. normal) | 0.780 | 0.448 | 3.03 | 0.082 | 2.18 [0.91; 5.25] | 1.04 |
| Cardiovascular disease | 0.543 | 0.338 | 2.58 | 0.108 | 1.72 [0.89; 3.34] | 1.37 |
| Positive family history (vs. none) | 0.476 | 0.235 | 4.10 | 0.043 | 1.61 [1.02; 2.55] | 1.17 |
| Family history unknown (vs. none) | 0.168 | 0.308 | 0.30 | 0.586 | 1.18 [0.65; 2.16] | 1.15 |
Simultaneous entry of predictors; indicator coding with reference categories: male sex, never smoked, normal glucose, no family history. Model: likelihood-ratio χ²(12) = 44.11, p < 0.001; Cox–Snell R² = 0.092; Nagelkerke R² = 0.123; McFadden R² = 0.070; AUC = 0.665; 18.6 events per predictor. B, regression coefficient; SE, standard error; VIF, variance inflation factor.
Table 8.
Design and governance requirements for an AI-enabled periodontal decision-support system derived from the three stakeholder surveys.
Table 8.
Design and governance requirements for an AI-enabled periodontal decision-support system derived from the three stakeholder surveys.
| Domain | Requirement | Supporting evidence from this study |
|---|---|---|
| Clinical scope | Prioritise early detection of gingivitis and screening of at-risk individuals; support monitoring of remission as a second-line function | Early gingivitis: 69.7% of dentists and 80.2% of physicians; remission monitoring requested more by dentists (54.5% vs. 27.5%) |
| Input data | Structured history-taking; photograph-based gingival assessment; radiographic markers (cortical plate, periodontal ligament space, bony pockets); glycaemic status, cardiovascular disease, stress, family history, smoking, hygiene | Automation of history-taking (81.8%) and visual assessment (72.7%); diabetes proposed by 81.8% of dentists; stress and family history independently associated with self-reported signs (aOR 2.11 and 1.61) |
| Target groups | Patients with diabetes, adults ≥ 65 years, smokers, workers in hazardous industries | Physicians’ priority groups: diabetes 71.4%, ≥ 65 years 62.6%, hazardous industries 52.7%, smokers 50.5% |
| Output | Graphical periodontal chart with colour-coded risk zones; ICD-coded text summary; probabilistic prognosis as optional layer; re-assessment of risk quarterly | Preferred formats: chart 66.7%, ICD-10 text 57.6%, probability 54.5%; re-assessment four times a year 72.7% |
| Human–AI interaction | Low autonomy: AI proposes, clinician verifies and decides; explicit verification step; no fully autonomous mode | All chosen autonomy options kept clinician control; experienced dentists demanded mandatory verification or prohibition of full autonomy (p = 0.045) |
| Transparency | Expose source data to the user; explain the reasoning; display the allocation of responsibility for each recommendation | Source data prioritised by less experienced dentists (53.3%), delimitation of responsibility by experienced dentists (50.0%) |
| Interprofessional use | Shared patient record and dashboard accessible to dentists and PHC physicians; simple screening mode for physicians without periodontal training | Physicians’ barriers: competence 53.8%, no simple tool 41.8%; dentists’ open-ended requests for “one database” |
| Governance | Clarify liability and insurance under the national AI law and health-care legislation before deployment; provide training and a usable interface | Leading barrier: no legal framework/insurance 60.6%; interface complexity 54.5%; distrust of output 51.5% |
| Measurement | Use locally validated self-report instruments; complement bleeding items with other symptoms in smokers | Six ad hoc symptom items not reliable (α = 0.56); smoking unrelated to bleeding but related to halitosis, suppuration and xerostomia |
aOR, adjusted odds ratio; PHC, primary health care.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.