

Submitted:
06 October 2026
Posted:
09 October 2026
You are already at the latest version
Abstract
Fetal growth restriction (FGR) is a major pregnancy complication linked to placental insufficiency, resulting from defective trophoblast differentiation, impaired maternal-fetal vascular adaptation, and altered nutrient sensing. This review synthesizes current evidence on the interconnected molecular networks driving placental dysfunction. We map the reciprocal crosstalk between the pro-inflammatory shift, highlighted by NLRP3 inflammasome-driven trophoblast pyroptosis, and dysregulated extracellular matrix remodeling mediated by the MMP-9/TIMP system. This hostile microenvironment feeds directly into the angiogenic imbalance defined by the sFlt-1/PlGF ratio, accelerating cellular senescence via p53 and disrupting survival hubs like the PTEN/PI3K/AKT axis. Consequently, downstream metabolic sensors, notably the mTOR pathway, are blunted, causing trafficking failure of essential amino acid (SNAT2, LAT1) and glucose (GLUT) transporters. Crucially, we introduce an original framework integrating emerging spatial transcriptomics and single-cell epigenomics, demonstrating that these pathomechanisms are anatomically regionalized rather than uniform. Finally, we provide a critical evaluation of translation-ready therapeutic targets, emphasizing that strict safety constraints against fetal teratogenesis render ligand-functionalized nanoparticles a non-negotiable prerequisite for placenta-selective drug delivery. Integrating molecular stratification with longitudinal biomarker profiling represents the next milestone for mechanism-based, targeted management of FGR.
Keywords:
fetal growth restriction
; placental insufficiency
; NLRP3 inflammasome
; angiogenesis
; mTOR signaling
; nutrient transport
; spatial transcriptomics
; targeted nanoparticles
1. Introduction
Fetal growth restriction (FGR), traditionally termed termed intrauterine growth restriction (IUGR), describes a fetus that does not achieve its biological growth potential and is associated with increased risks of perinatal morbidity, mortality, and later-life disease [1,2]. Although estimated fetal weight or abdominal circumference below the 10th percentile is frequently used in clinical assessment, fetal smallness is not synonymous with pathological growth restriction; constitutionally small fetuses may be healthy, whereas FGR reflects an underlying pathological process [3,4]. FGR is multifactorial and may reflect maternal disease, fetal genetic or structural abnormalities, infection, environmental exposures, or placental pathology, with placental dysfunction representing a major mechanism in a substantial proportion of cases [5,6]. Normal placental function requires coordinated trophoblast differentiation and invasion, remodeling of the maternal spiral arteries, development of the villous vascular tree, and establishment of efficient maternal–fetal exchange. Inadequate placentation can leave the uteroplacental circulation with excessive vascular resistance and heterogeneous perfusion, reducing the capacity of the placenta to deliver oxygen and nutrients and to remove fetal metabolic waste [5,7].
Structural and functional abnormalities of the trophoblast, villi, and fetoplacental vessels are therefore central to the pathophysiology of placental FGR [8]. Clinical surveillance combines serial assessment of fetal growth with Doppler velocimetry and other fetal well-being measures, while delivery is individualized according to gestational age, fetal condition, and the severity of placental dysfunction [2,4].
At the molecular level, FGR is best understood as a network disorder of the maternal–placental–fetal interface. Persistent inflammatory signaling can alter trophoblast proliferation, differentiation, invasion, and vascular function, while activation of the NLRP3 inflammasome may promote caspase-dependent inflammatory cell death and amplify placental injury [9]. In parallel, dysregulated extracellular matrix remodeling can interfere with trophoblast invasion and spiral artery remodeling. MMP-9 is particularly relevant because its activity contributes to matrix turnover and placental remodeling, although the direction and magnitude of its alteration appear to depend on tissue, gestational age, and FGR phenotype [10,11].
Angiogenic and growth factor pathways provide another major layer of regulation. VEGF and PlGF support placental vascular development, whereas sFlt-1 reduces the bioavailability of these pro-angiogenic factors; altered concentrations of PlGF and sFlt-1/PlGF have been associated with placental dysfunction and FGR [12,13,14]. TGF-β family signaling contributes to trophoblast differentiation and extracellular matrix organization, while the IGF/IGFBP system regulates trophoblast growth, survival, nutrient transport, and fetal growth. Cellular fate and chromatin dynamics are similarly important; p53 regulates cell-cycle arrest and apoptosis, PTEN constrains PI3K/AKT signaling, and ARID1A modifies chromatin accessibility and trophoblast transcriptional programs [15,16,17].
Crucially, the placenta acts as a dynamic mediator that links the maternal environment to the fetus through sophisticated epigenetic modifications and metabolic sensing pathways. Epigenetic and genomic regulation—encompassing DNA methylation, histone modifications, ATP-dependent chromatin remodeling, and non-coding RNAs—enables the fine-tuning of gene networks essential for trophoblast development and vascular adaptation [18,19]. When these epigenetic mechanisms are disrupted, placental metabolic signaling and nutrient transport are directly compromised. This includes severe alterations in key amino acid transport systems, such as System A (SNAT2) and System L (LAT1), as well as glucose transporter (GLUT) expression and trafficking, which collectively reduce the transport capacity of the placenta and restrict fetal growth [20,21]. Evidence from human placentas and experimental models suggests that these pathways do not operate in isolation but form an integrated, self-reinforcing pathological network [15,16,17].
The aim of this review is to provide a focused synthesis of the molecular mechanisms of placental dysfunction in FGR. We underscore the interplay among inflammation, extracellular matrix remodeling, angiogenesis, and growth factor signaling, while integrating recent insights into tumor suppressor pathways, epigenetic and genomic regulation, and placental metabolic and nutrient transport pathways. Finally, we discuss how these interconnected molecular networks may inform biomarker development and future mechanism-based therapeutic interventions.
2. Search Strategy
A structured narrative literature search was conducted to identify evidence on the molecular, cellular, and placental mechanisms involved in FGR, with emphasis on the biological domains addressed in this review.
2.1. Information Sources and Search Period
Electronic searches were performed in PubMed/MEDLINE, Scopus, Web of Science, and Google Scholar for publications from 2000 through 30 September 2026. Reference lists of relevant reviews and primary studies were also screened to identify additional eligible publications contained within the existing bibliography of the original manuscript.
2.2. Core FGR and Placental Terms
The core search combined “fetal growth restriction,” “FGR,” “fetal growth retardation,” “intrauterine growth restriction,” “IUGR,” “small for gestational age,” “SGA,” “fetal growth,” “placental insufficiency,” “placental dysfunction,” “placenta,” “trophoblast,” “maternal–fetal interface,” “maternal vascular malperfusion,” and “fetal vascular malperfusion”.
2.3. Molecular and Biological Domains
Inflammation and immune signaling were searched using “inflammation,” “placental inflammation,” “cytokines,” “TNF-α,” “IL-1β,” “IL-6,” “IL-10,” “NF-κB,” “NLRP3,” “inflammasome,” “caspase-1,” and “pyroptosis.” Extracellular matrix and trophoblast remodeling searches included “MMP-9,” “TIMP-1,” “extracellular matrix,” “trophoblast invasion,” “trophoblast migration,” “spiral artery remodeling,” and “placental remodeling”.
2.3.1. Angiogenesis and Vascular Signaling
Searches included “angiogenesis,” “placental angiogenesis,” “VEGF,” “VEGFA,” “PlGF Bars,” “VEGFR,” “sFlt-1,” “soluble endoglin,” “vascular remodeling,” “endothelial dysfunction,” and “uteroplacental perfusion”.
2.3.2. Growth Factor and Trophoblast Signaling
Searches included “TGF-α,” “TGF-β,” “TGF-β2,” “EGFR,” “insulin-like growth factor,” “IGF-1,” “IGF-2,” “IGF1R,” “IGF2R,” “IGFBP-1,” “IGFBP-2,” “IGFBP-3,” “IGFBP-4,” and “IGFBP-5”.
2.3.3. Tumor Suppressor Pathways
Searches included “p53,” “TP53,” “PTEN,” and “ARID1A”.
2.3.4. Metabolic Signaling and Nutrient Transport
Searches included “metabolic signaling,” “SNAT2,” “LAT1,” “GLUT1,” “GLUT3,” “GLUT4,” “nutrient transport,” and “amino acid transport”.
2.3.5. Epigenetic and Genomic Regulation
Searches included “epigenetics,” “DNA methylation,” “histone modification,” “chromatin remodeling Bars,” “SWI/SNF,” “microRNA,” “miRNA,” “non-coding RNA,” “gene expression,” and “transcriptional regulation”.
2.4. Search Structure and Eligibility
The principal concepts were combined with AND/OR operators, using phrase searching and truncation where supported. Eligible evidence included human pregnancy studies, placental tissue analyses, maternal or fetal biological samples, trophoblast or placental cell models, and relevant experimental animal studies. Studies were prioritized when they directly investigated FGR or placental insufficiency and provided mechanistic information relevant to the pathways addressed in the review.
2.5. Study Selection and Evidence Synthesis
Titles and abstracts were screened first, followed by full-text assessment when appropriate. Evidence was synthesized narratively and organized into specific clinical and molecular subsections: inflammation, extracellular matrix remodeling, angiogenesis, growth factor signaling, tumor suppressor pathways, epigenetic regulation, and placental metabolic signaling and nutrient transport. Human and experimental evidence were considered separately where appropriate, and mechanistic interpretations were not treated as equivalent to validated clinical biomarkers or established therapies.
3. Inflammation-Driven Placental Dysfunction in FGR
3.1. Cytokines as Mediators of Placental Inflammation and FGR
In recent years, increasing data indicate that alterations in maternal, fetal and placental inflammatory responses play a crucial role in the pathophysiology of FGR pregnancy [22]. Central to these processes are cytokines, a heterogeneous group of small secreted proteins (<40 kDa), which regulate the immune response through the activation, recruitment and differentiation of various types of immune cells. Cytokines are produced mainly by activated macrophages, but also by other cells of the immune system [23,24]. Based on their function, cytokines are divided into pro-inflammatory and anti-inflammatory. Pro-inflammatory cytokines include, among others, tumor necrosis factor-α (TNF-α), interleukin-1β (IL-1β), interleukin-6 (IL-6), interleukin-8 (IL-8) and interferon-γ (IFN-γ), which enhance the inflammatory response and contribute to the activation of innate and adaptive immune mechanisms [25]. In contrast, anti-inflammatory cytokines, such as interleukin-1 receptor antagonist (IL-1Ra), transforming growth factor-β (TGF-β), interleukin-4 (IL-4), interleukin-10 (IL-10), and interleukin-13 (IL-13), act inhibitory against pro-inflammatory signals, contributing to the maintenance of immune balance [26].
IL-10 is a key anti-inflammatory cytokine with a crucial role during pregnancy. In normal pregnancies, it contributes to maintaining the immune balance between mother and fetus, suppresses excessive inflammatory responses, and supports the integrity of the placental vascular network. Through these actions, it enhances the normal function of the placenta and promotes normal fetal development [27,28]. In contrast, in pregnancies complicated by FGR, a significant decrease in IL-10 levels has been reported in the maternal, fetal and placental environment, which is accompanied by increased expression of proinflammatory cytokines, such as TNF-α, IL-6, IL-8, IL-18 and IL-1β [28,29]. This imbalance between anti-inflammatory and pro-inflammatory factors is associated with the development of placental inflammation, impaired proliferation and invasive capacity of trophoblast cells, increased, and reduced placental vascularity [30,31] (Figure 1).
Overall, the evidence suggests that dysregulation of the maternal–fetal immune balance in FGR promotes a pro-inflammatory placental environment that may impair placental function and compromise fetal growth and development. The investigation of the interactions between pro-inflammatory and anti-inflammatory cytokines is expected to provide important information for the identification of new diagnostic markers and the development of targeted prevention and treatment strategies. Nevertheless, the full elucidation of the molecular mechanisms involved and the documentation of the clinical efficacy of interventions that modify the action of cytokines require further experimental and clinical research.
3.2. The Emerging Role of Adipokines in Placental Dysfunction and FGR
Adipokines are bioactive proteins secreted mainly by adipose tissue and play an important role in the regulation of energy metabolism, glucose homeostasis and inflammatory processes. Based on their biological activity, they are distinguished into pro-inflammatory and anti-inflammatory adipokines [32]. The pro-inflammatory adipokines include leptin, visfatin, resistin and plasminogen activator inhibitor-1 (PAI-1), while adiponectin and apelin are among the adipokines with anti-inflammatory and cytoprotective properties [33].
During pregnancy, the progressive increase in fat mass and the accompanying metabolic and endocrine adaptations significantly affect the production and action of adipokines [34]. Thus, their study in pregnancies complicated by FGR is of particular interest, as it may contribute to the understanding of the underlying pathophysiological mechanisms and the identification of new biomarkers and therapeutic targets.
In healthy pregnancies, adiponectin participates in the regulation of nutrient transport across the placenta and influences cell signaling pathways that are essential for the normal fetal development [35]. At the same time, apelin contributes to the regulation of angiogenesis, energy metabolism and inflammatory response, supporting the functional adequacy of the placenta and fetal development [36,37].
In fetal growth restriction (FGR) pregnancies, reduced concentrations of both adiponectin and apelin have been reported in the maternal circulation and placental tissue compared to appropriate-for-gestational-age (AGA) controls [35,37]. This downregulation directly correlates with heightened inflammatory activity and impaired placental function [35,37] (Figure 2).
Conversely, several proinflammatory adipokines—including leptin, visfatin, resistin, plasminogen activator inhibitor-1 (PAI-1), chemerin, and fatty acid-binding protein 4 (FABP-4)—exhibit upregulated expression or elevated concentrations within the maternal and fetal circulation, as well as the placenta, during conditions of placental dysfunction and compromised fetal development [38]. These adipokines appear to exacerbate the inflammatory response, promote endothelial dysfunction, and adversely affect placental function, thereby contributing to the restriction of fetal growth [39,40] (Figure 2).
Overall, the data to date indicate that FGR pregnancies are characterized by a disruption of the balance between anti-inflammatory and pro-inflammatory adipokines, which favors the creation of a pro-inflammatory microenvironment in the placenta. The reduced presence of protective adipokines, combined with the increased expression of pro-inflammatory mediators, may contribute to placental dysfunction and inadequate fetal growth. Further investigation of the role of adipokines in the pathophysiology of FGR could lead to the development of new diagnostic and prognostic biomarkers, as well as innovative therapeutic interventions. However, more experimental and clinical studies are needed to fully elucidate their biological and clinical significance.
3.3. NLRP3 Inflammasome Activation as a Driver of Inflammation, Pyroptosis, and Placental Dysfunction in FGR
The NLRP3 inflammasome is an intracellular multiprotein complex of innate immunity that activates caspase-1 and promotes maturation of IL-1β and IL-18 [41,42]. In healthy pregnancy, controlled inflammasome activity contributes to local immune surveillance and placental adaptation, whereas excessive activation may disturb trophoblast and vascular function [43,44] (Figure 3).
In FGR, increased placental NLRP3 activation has been accompanied by higher caspase-1, IL-1β and IL-18 expression. Activation of the NLRP3/caspase-1 axis can promote gasdermin-D-dependent pyroptosis and release of inflammatory mediators, thereby impairing trophoblast proliferation, migration and invasion. These changes may interfere with spiral-artery remodeling and placental vascular development and contribute to placental insufficiency [45,46] (Figure 3).
Overall, current evidence supports NLRP3 inflammasome activation as an important inflammatory mechanism in FGR. Its association with altered cytokine production and trophoblast, cell death makes the pathway a potential biomarker and experimental therapeutic target, although its diagnostic value and clinical safety require further validation.
3.4. Inflammation-Mediated Placental Remodeling and MMP-9 Signaling
MMP-9 is a key proteolytic enzyme involved in extracellular matrix (ECM) degradation, trophoblast invasion, angiogenesis, and placental tissue remodeling during normal pregnancy [47]. Expressed by trophoblasts, MMP-9 facilitates extravillous trophoblast invasion by degrading basement membrane components, including type IV collagen and laminin, thereby contributing to spiral artery remodeling and the establishment of adequate uteroplacental perfusion [50,51,52,53,54,55,56,57,58]. Through its effects on trophoblast migration, differentiation, and vascular remodeling, MMP-9 contributes to the development of a functional placental vascular network essential for adequate fetal oxygen and nutrient supply [51].
In FGR, placental MMP-9 expression and activity appear to be dysregulated and have been associated with impaired trophoblast invasion, incomplete spiral-artery remodeling and altered placental vascularization [50,52,53]. Altered MMP-9/TIMP-1 balance may influence extracellular-matrix turnover and the local availability of cytokines and growth factors. Because MMP-9 activity varies according to tissue compartment, gestational age and disease phenotype, its contribution should be interpreted within the broader process of placental remodeling rather than as an isolated biomarker.
Hypoxia and inflammatory signaling may further modify MMP-9 regulation through NF-κB, AP-1 and HIF-dependent pathways. The resulting imbalance in extracellular-matrix turnover may impair trophoblast invasion, spiral-artery remodeling and development of the fetoplacental vascular network [50].
MMP-9 also plays an important role in angiogenic remodeling by modifying the ECM and increasing the bioavailability of matrix-sequestered proangiogenic factors, particularly VEGF [54]. Dysregulated MMP-9 activity may therefore contribute to alterations in the local angiogenic environment and the imbalance between pro- and antiangiogenic factors characteristic of placental dysfunction. Such changes may impair placental vascular development and ultimately compromise fetal oxygen and nutrient exchange [55,56,57]. The biological effects of MMP-9 are further determined by its balance with tissue inhibitors of metalloproteinases (TIMPs), particularly TIMP-1. In human FGR placentas, reduced MMP-9 expression together with increased TIMP-1 and TIMP-3 expression has been reported, suggesting altered proteolytic balance and impaired ECM remodeling [58,59].
Overall, dysregulation of the MMP-9/TIMP system in FGR may represent a convergence point between ECM remodeling, trophoblast invasion, inflammation, hypoxia, and angiogenesis. Rather than acting as an isolated mediator, MMP-9 may therefore participate in a broader pathological network that compromises placental structure and function and contributes to FGR. These interconnected pathways also identify MMP-9 and its regulatory mechanisms as potential targets for further investigation in FGR.
4. The Role of Growth-Factor and Angiogenic Dysregulation in the Pathophysiology of FGR
4.1. Placental Growth Factor (PlGF) as a Key Regulator of Healthy and FGR Pregnancies
Placental Growth Factor (PlGF) is an important member of the vascular endothelial growth factor (VEGF) family and actively participates in the regulation of angiogenesis in the human placenta through its binding to the VEGFR-1 receptor, for which it displays high affinity [60,61]. Its production occurs mainly by the syncytiotrophoblast and its secretion into the maternal circulation makes PlGF an important factor for the normal development of pregnancy [62].
PlGF contributes to the maintenance of pregnancy, regulating the distribution of nutrients between the mother and fetus. In particular, it affects both the availability of nutrients to the mother and their transport to the fetus, playing a crucial role in uteroplacental function [63]. At the same time, its action is linked to placental development, the normal adaptation of the maternal organism during pregnancy and fetal development through interactions with the insulin-like growth factor-I (IGF-I) signaling pathways and the regulation of maternal metabolism [64,65] (Figure 4).
Reduced concentrations of PlGF in the maternal circulation have been associated with FGR. One possible mechanism involves dysfunction of the growth hormone/insulin-like growth factor-I (GH/IGF-I) axis, which may limit fetal growth and contribute to the occurrence of FGR pregnancy [64,65]. Furthermore, it has been reported that FGR pregnancies exhibit significantly lower levels of PlGF in the maternal circulation compared to healthy pregnancies [66] (Figure 4).
The study by Hong and Kumar suggests that PlGF is one of the most promising circulating markers of placental dysfunction, with potential value in the early prediction and recognition of FGR [67]. Although the data to date support its utility as a biomarker of placental function, further research is required to fully understand the molecular mechanisms through which PlGF influences fetal development, as well as to confirm its clinical application in the prognosis and management of FGR.
4.2. VEGF Signaling in Placental Vascular Development and Angiogenic Dysfunction
Vascular endothelial growth factor is one of the most important regulators of angiogenesis in the placenta. Its biological action is exerted mainly through its binding to the VEGFR-1 (Flt-1) and VEGFR-2 (KDR) receptors, which activate molecular pathways that promote the proliferation, migration, survival and remodeling of endothelial cells, contributing to the creation and maintenance of a functional vascular network in the placenta [68,69]. Normal VEGF signaling is essential for adequate placental vascularization, while disturbances in its expression or activity have been associated with placental insufficiency and FGR [70].
During healthy pregnancy, VEGF is expressed in various cell populations of the placenta, including cytotrophoblasts, syncytiotrophoblasts, and placental vascular endothelial cells. The wide distribution of both VEGF and its receptors suggests that this factor exerts autocrine and paracrine actions, which are essential for the normal function of trophoblast cells and the development of the placental vascular network [69,71] (Figure 5).
In pregnancies complicated by FGR, impaired VEGF signaling and reduced expression of its receptors, particularly VEGFR-2 (KDR), have been observed, reflecting impaired angiogenic activity and inadequate development of the placental vascular network [72]. Furthermore, gene expression studies have revealed significant alterations in genes and microRNAs involved in the regulation of angiogenesis in the placentas of FGR, suggesting that disrupted angiogenic pathways contribute to the pathological formation of placental vascular architecture and the reduction of blood flow to the fetus [73] (Figure 5).
Hypoxia, which is a hallmark of placental insufficiency, also affects the regulation of VEGF and related angiogenic factors [75]. Under conditions of low oxygenation, the balance between proangiogenic and antiangiogenic factors is altered, leading to further deterioration of placental function [76]. At the same time, placentas associated with FGR exhibit reduced expression of VEGF in combination with increased levels of the antiangiogenic factor sFlt-1 and increased markers of, such as malondialdehyde (MDA) and 8-hydroxy-2΄-deoxyguanosine (8-OHdG) [77]. These findings support the existence of a close interaction between angiogenic imbalance, and hypoxia in the pathogenesis of FGR.
Overall, VEGF is a fundamental regulator of placental angiogenesis and AGA fetal development. Reduced VEGF activity, impaired expression of its receptors, disruption of angiogenic gene networks, and the effects of hypoxia, contribute to placental dysfunction and reduced uteroplacental perfusion. Therefore, impaired VEGF signaling is considered one of the key mechanisms linking placental insufficiency to FGR. A deeper understanding of these molecular mechanisms may contribute to the development of new diagnostic biomarkers and therapeutic approaches to improve placental function and fetal outcome in high-risk pregnancies.
4.3. The TGF-α/EGFR Signaling Pathway in Placental Development and FGR
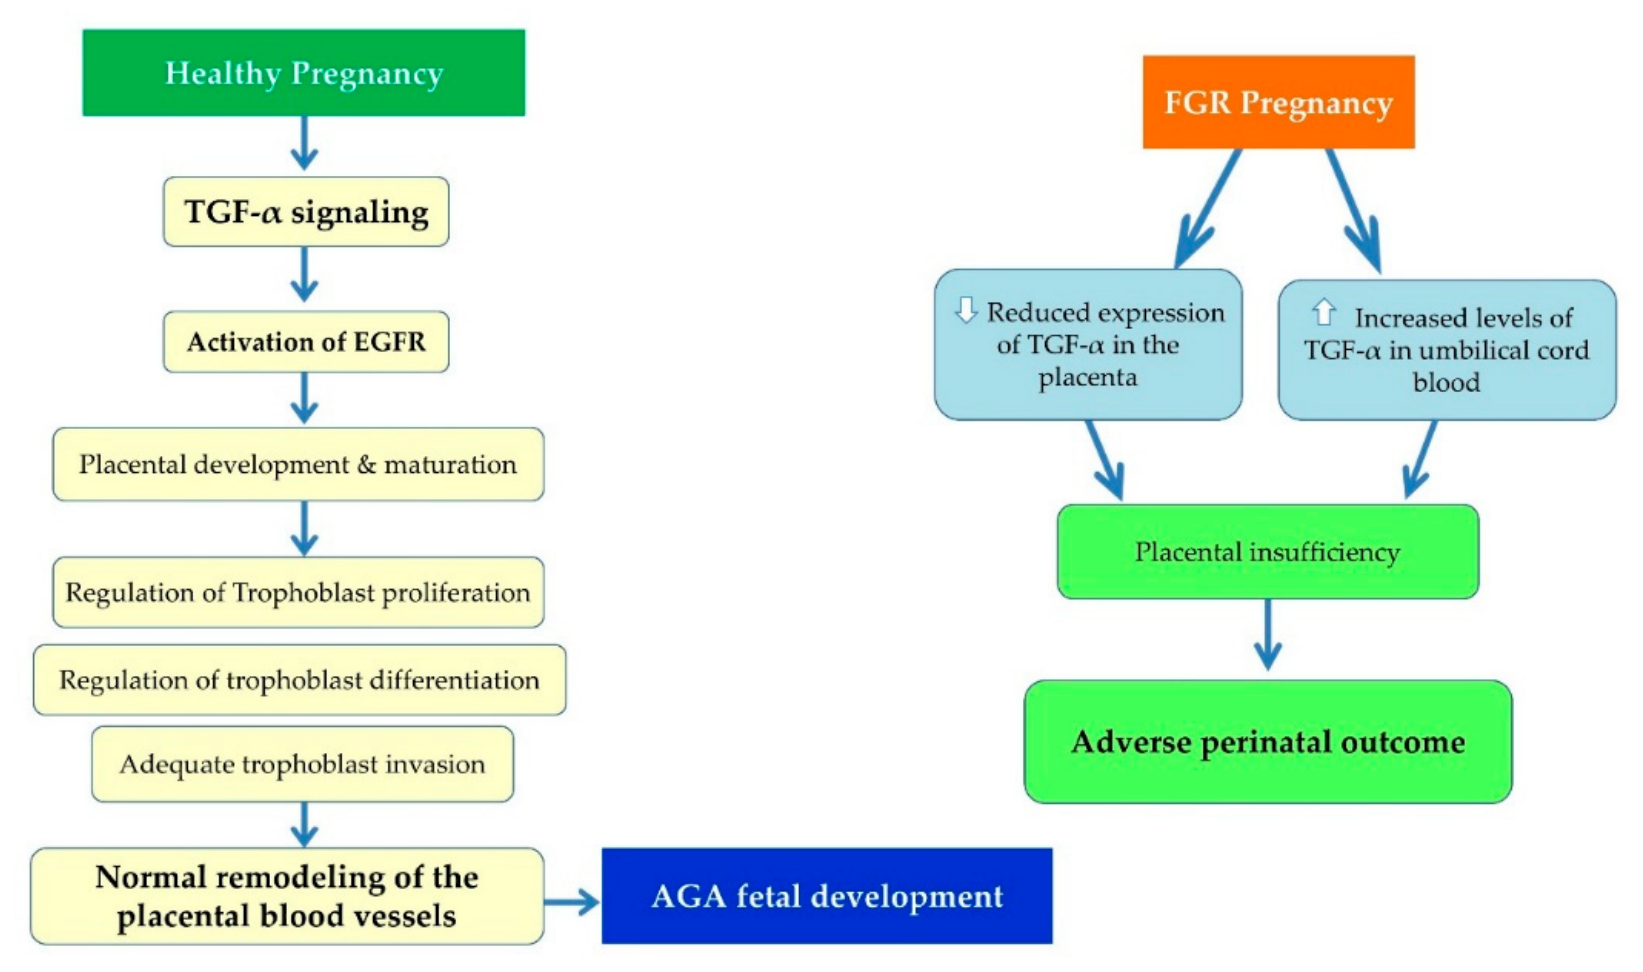
TGF-α is a member of the epidermal growth factor (EGF) family, which is involved in the regulation of cell proliferation, differentiation and angiogenesis [78]. Current research data indicate that disruption of TGF-α expression and action in the placenta may contribute to placental dysfunction and, by extension, to FGR [79]. During healthy pregnancy, TGF-α is expressed in placental trophoblast cells and it has been shown that its exogenous administration stimulates their proliferation, thus enhancing placental growth and maturation [80]. Its biological action is exerted mainly through interaction with the epidermal growth factor receptor (EGFR), activating signaling pathways that regulate the proliferation, differentiation, invasion, and fusion of trophoblast cells. These processes are essential for the proper formation of the placenta and the remodeling of its vascular network [79] (Figure 5).
In pregnancies complicated by FGR increased concentrations of TGF-α have been observed in cord blood compared with AGA neonates. These findings suggest alterations in the regulation of this growth factor and possible dysfunction of placental growth mechanisms [81]. At the same time, the expression of TGF-α, EGF and other members of the EGF family of growth factors appears reduced in the placental tissue of pregnancies with FGR, which supports the view that the attenuation of the relevant signaling contributes to the occurrence of placental insufficiency [79]. Insufficient activation of these pathways may negatively affect the functionality of trophoblast cells and limit normal vascular development of the placenta (Figure 5).
Overall, TGF-α plays a crucial role in the normal development and function of the placenta, as it participates in the regulation of trophoblast proliferation, differentiation and invasive capacity, as well as in vascular remodeling through the activation of EGFR. In FGR, a disruption of the TGF-α/EGFR pathway is observed, which is manifested by increased levels of TGF-α in the fetal circulation but reduced expression in the placenta. These changes may contribute to trophoblast cell dysfunction, impaired angiogenesis, and the development of placental insufficiency, ultimately leading to FGR. A deeper understanding of the role of TGF-α in placental biology and the mechanisms of its dysregulation in FGR could contribute to the development of new biomarkers and therapeutic interventions aimed at improving fetal outcome in high-risk pregnancies.
Figure 6.
Schematic illustration of the role of TGF-α in heathly and FGR pregnancy; (abbreviation, TGF-α: Transforming Growth Factor-alpha; EGFR: Epidermal Growth Factor Receptor; AGA: Appropriate for Gestational Age; FGR: Fetal Growth Restriction).
Figure 6.
Schematic illustration of the role of TGF-α in heathly and FGR pregnancy; (abbreviation, TGF-α: Transforming Growth Factor-alpha; EGFR: Epidermal Growth Factor Receptor; AGA: Appropriate for Gestational Age; FGR: Fetal Growth Restriction).
4.4. The Role of Transforming Growth Factor-beta 2 (TGF-β2) in Placental Development and FGR
Transforming growth factor-beta 2 (TGF-β2) is a multifunctional cytokine and growth factor belonging to the TGF-β superfamily that contributes to cell differentiation, immunomodulation, extracellular matrix remodeling, and placental development [82]. In the human placenta, TGF-β2 is expressed at the maternal–fetal interface and is involved in the regulation of trophoblast function, including proliferation, differentiation, and invasion [82,83]. TGF-β2 expression in the human placenta appears to be the predominant TGF-β isoform during the third trimester, with expression localized to trophoblast populations, the chorionic plate, the decidua, and the placental basal plate. Its tightly regulated signaling may therefore contribute to placental homeostasis and trophoblast function [82]. During early human placentation, TGF-β2 negatively regulates extravillous trophoblast (EVT) invasion and outgrowth and contributes to the regulation of endovascular EVT differentiation and spiral artery remodeling [84,85,86]. In parallel, TGF-β2 may contribute to maternal–fetal immune tolerance by participating in the immunoregulatory milieu at the maternal–fetal interface, while TGF-β signaling more broadly promotes regulatory T-cell differentiation and modulates uterine/decidual natural killer-cell function [82,87,88]. Also, TGF-β2 is involved in regulating trophoblast function, placental vascular development, angiogenesis, and extracellular matrix remodeling through SMAD-dependent and non-canonical pathways, while interacting with broader angiogenic and matrix-remodeling mechanisms that contribute to placental function [86,88,89].
Dysregulated TGF-β/SMAD2/3 signaling may impair trophoblast function and contribute to FGR [88,90,91]. Altered TGF-β2 signaling may also disturb extracellular-matrix remodeling within the placenta, potentially affecting trophoblast differentiation, vascular development and tissue architecture [82].
Overall, TGF-β2 emerges as an important component of the regulatory network governing trophoblast behavior, maternal–fetal immune homeostasis, extracellular matrix remodeling, and placental vascular adaptation. In FGR, the hypoxic and inflammatory placental environment may alter TGF-β signaling and its downstream SMAD-dependent pathways, potentially disrupting the coordinated regulation of trophoblast invasion, extracellular matrix remodeling, and vascular function. Such dysregulation may contribute to abnormal placental architecture, endothelial dysfunction, and impaired placental homeostasis, providing a potential mechanistic link between altered TGF-β signaling and FGR.
4.5. The Insulin-like Growth Factor (IGF) System in Placental Development and FGR
AGA fetal development is largely dependent on the IGF system, which comprises IGF-I and IGF-II, their receptors (primarily IGF-IR and IGF-IIR), and six insulin-like growth factor-binding proteins (IGFBP-1 to IGFBP-6) [92]. This system is a major regulator of placental and fetal development and controls critical cellular processes, including proliferation, differentiation, survival, apoptosis, and angiogenesis [93.94]. IGFBPs regulate the bioavailability, distribution, and activity of IGFs and can also exert IGF-independent effects that influence cellular growth, inflammation, and cellular stress responses [95].
In the normal placenta, both IGF-I and IGF-II are expressed and contribute to placental growth, trophoblast function, and maintenance of placental tissue homeostasis [93]. IGF signaling is important for trophoblast proliferation and survival, placental vascular development, and the regulation of nutrient and oxygen supply to the fetus [93,96]. In parallel, the regulated expression and activity of IGFBPs contribute to the control of local IGF bioavailability and to placental homeostasis and fetal growth [97].
Increasing evidence indicates that dysregulation of the IGF system is involved in the pathogenesis of FGR [98]. In pregnancies complicated by FGR, reduced IGF-I expression and/or signaling has been reported in placental tissue and fetal circulation, and lower fetal IGF-I concentrations are associated with reduced birth weight [99,100]. In contrast, IGF-II expression and signaling appear to be more complex and may vary according to placental tissue, gestational age, and the underlying cause of FGR; therefore, altered rather than uniformly reduced IGF-II signaling is a more appropriate description [93,100,101]. Experimental and human studies indicate that impaired IGF signaling may affect trophoblast proliferation and survival, placental angiogenesis, and nutrient transport, thereby contributing to placental insufficiency and FGR [93,101,102].
Recent evidence has further highlighted the potential involvement of specific Insulin-like Growth Factor-I (IGF-I) splice isoforms, particularly IGF-IEa and IGF-IEb, in the placental dysfunction associated with FGR. Interestingly, both isoforms share a common transcriptional profile: recent studies by Fasoulopoulos et al. demonstrated that neither total placental IGF-IEa (2025) [103] nor IGF-IEb (2026) [104] mRNA levels differ significantly between FGR and AGA pregnancies. However, at the protein level, they undergo highly dynamic, isoform- and compartment-specific regulation, exhibiting distinct immunoreactivity patterns that reflect different underlying pathological or adaptive mechanisms [103,104].
Specifically, for the IGF-IEa isoform, protein immunoreactivity is frequently reduced or entirely absent in the extravillous trophoblasts of FGR placentas, a localized loss that correlates with histological features of maternal malperfusion and suggests a direct link to defective placentation [103]. Conversely, the IGF-IEb isoform exhibits increased protein expression in the perivillous syncytiotrophoblast, which correlates with maternal vascular malperfusion and specific clinical parameters such as gestational age, neonatal birth weight, placental weight, and fetal sex [104]. Despite these contrasting shifts in the trophoblast compartments, both isoforms demonstrate a common increased immunoreactivity within the endothelium of fetal villous and maternal decidual vessels in FGR [103,104]. This vascular upregulation potentially reflects a shared, localized adaptive response of the placenta to vascular insufficiency and hypoxia, aimed at promoting angiogenesis and vasodilation to counteract malperfusion.
Importantly, the striking discrepancy between unchanged mRNA expression and altered protein distribution strongly points toward complex post-transcriptional regulatory mechanisms governing both isoforms in the presence of altered local signaling [103,104]. Nevertheless, the available evidence remains strictly observational and does not establish a causal or direct functional role for either IGF-IEa or IGF-IEb in the development of FGR. Further mechanistic, functional, and prospective studies are therefore required to fully determine whether these isoforms represent clinically useful biomarkers of placental dysfunction or active molecular mediators of placental tissue adaptation [103,104].
Increased circulating IGFBP-1 concentrations and enhanced site-specific phosphorylation of IGFBP-1 have been reported in pregnancies complicated by FGR, particularly in fetal and umbilical cord blood. Increased phosphorylation of IGFBP-1 at specific serine residues, including Ser101, Ser119, and Ser169, increases its affinity for IGF-I and may promote IGF-I sequestration, thereby reducing IGF-I bioavailability and IGF-I receptor signaling [105,106]. Experimental studies further indicate that hypoxia and nutrient deprivation can promote IGFBP-1 hyperphosphorylation, providing a potential mechanistic link between the adverse intrauterine environment, altered IGF-I bioavailability, and FGR [106,107]. In addition, altered expression and proteolytic processing of IGFBPs may modify local IGF bioavailability at the maternal–fetal interface and contribute to abnormal placental function [99]. IGFBP-4 and IGFBP-5 are expressed in the developing placenta and can modulate IGF-dependent trophoblast migration and invasion. Experimental evidence indicates that IGFBP-4 and IGFBP-5 may also exert IGF-independent effects on placental cellular processes, although their specific contribution to human FGR remains incompletely defined [108,109]. The IGF/IGFBP system is closely integrated with inflammatory pathways, which influence IGF bioavailability and trophoblast may function in FGR [110]. Increased IL-6 concentrations have been reported alongside altered IGFBP-1 and IGFBP-2 levels, suggesting that inflammatory signaling may modify growth-factor activity within the placenta [100].
Overall, the IGF/IGFBP system plays a central role in regulating placental function and fetal development. In FGR pregnancy, dysregulation of IGF-I, IGF-II, and IGFBPs is closely associated with abnormalities in trophoblast function, placental development, inflammation and may contribute to placental insufficiency and FGR. Further characterization of these molecular interactions may help identify biomarkers of placental dysfunction and improve understanding of potential therapeutic targets for FGR.
4.6. Angiogenic Imbalance and the Role of sFlt-1 in FGR
Disturbed placentation and dysfunction of the placental vascular network are key pathophysiological mechanisms of FGR [111,112,113,114]. One of the most important antiangiogenic factors associated with placental insufficiency is the sFlt-1, which is considered an indicator of a disruption in the balance between angiogenic and antiangiogenic factors in the placenta [115]. sFlt-1 functions as a circulating decoy receptor for VEGF and PlGF, binding to these factors and thereby reducing their bioavailability. As a result, the normal development of the placental vascular network is restricted and angiogenesis is disrupted, which contributes to the occurrence of placental dysfunction [116].
In pregnancies complicated by FGR, increased values of the sFlt-1/PlGF ratio in maternal serum have been recorded, a finding that reflects the presence of placental insufficiency. Systematic analyses including more than 25,000 pregnancies have shown that women with FGR consistently present higher values of the sFlt-1/PlGF ratio compared to pregnancies with AGA growing fetuses [115,117,118]. A similar increase is observed in preeclampsia, although the levels of the sFlt-1/PlGF ratio are usually higher in preeclampsia than in FGR, suggesting that the two conditions share a common background of angiogenic dysregulation but with different severity [115,117,118]. Furthermore, elevated levels of sFlt-1 and the sFlt-1/PlGF ratio are associated with reduced concentrations of free VEGF and PlGF, endothelial dysfunction, and reduced uteroplacental perfusion [115]. In contrast, in healthy pregnancies, a gradual increase in sFlt-1 levels is observed during the third trimester, which is considered part of the normal regulation of angiogenesis and does not negatively affect fetal development [119].
Overall, elevated sFlt-1 levels in maternal and placental tissue of FGR pregnancies reflect impaired placental angiogenic balance and contribute to endothelial dysfunction and reduced uteroplacental perfusion. These data support that sFlt-1 is not only a key mediator of placental insufficiency but also a promising biomarker for the assessment of angiogenic dysregulation in FGR, distinct from the normal changes observed during pregnancy.
5. Tumor Suppressor and Chromatin-Regulatory Pathways in FGR
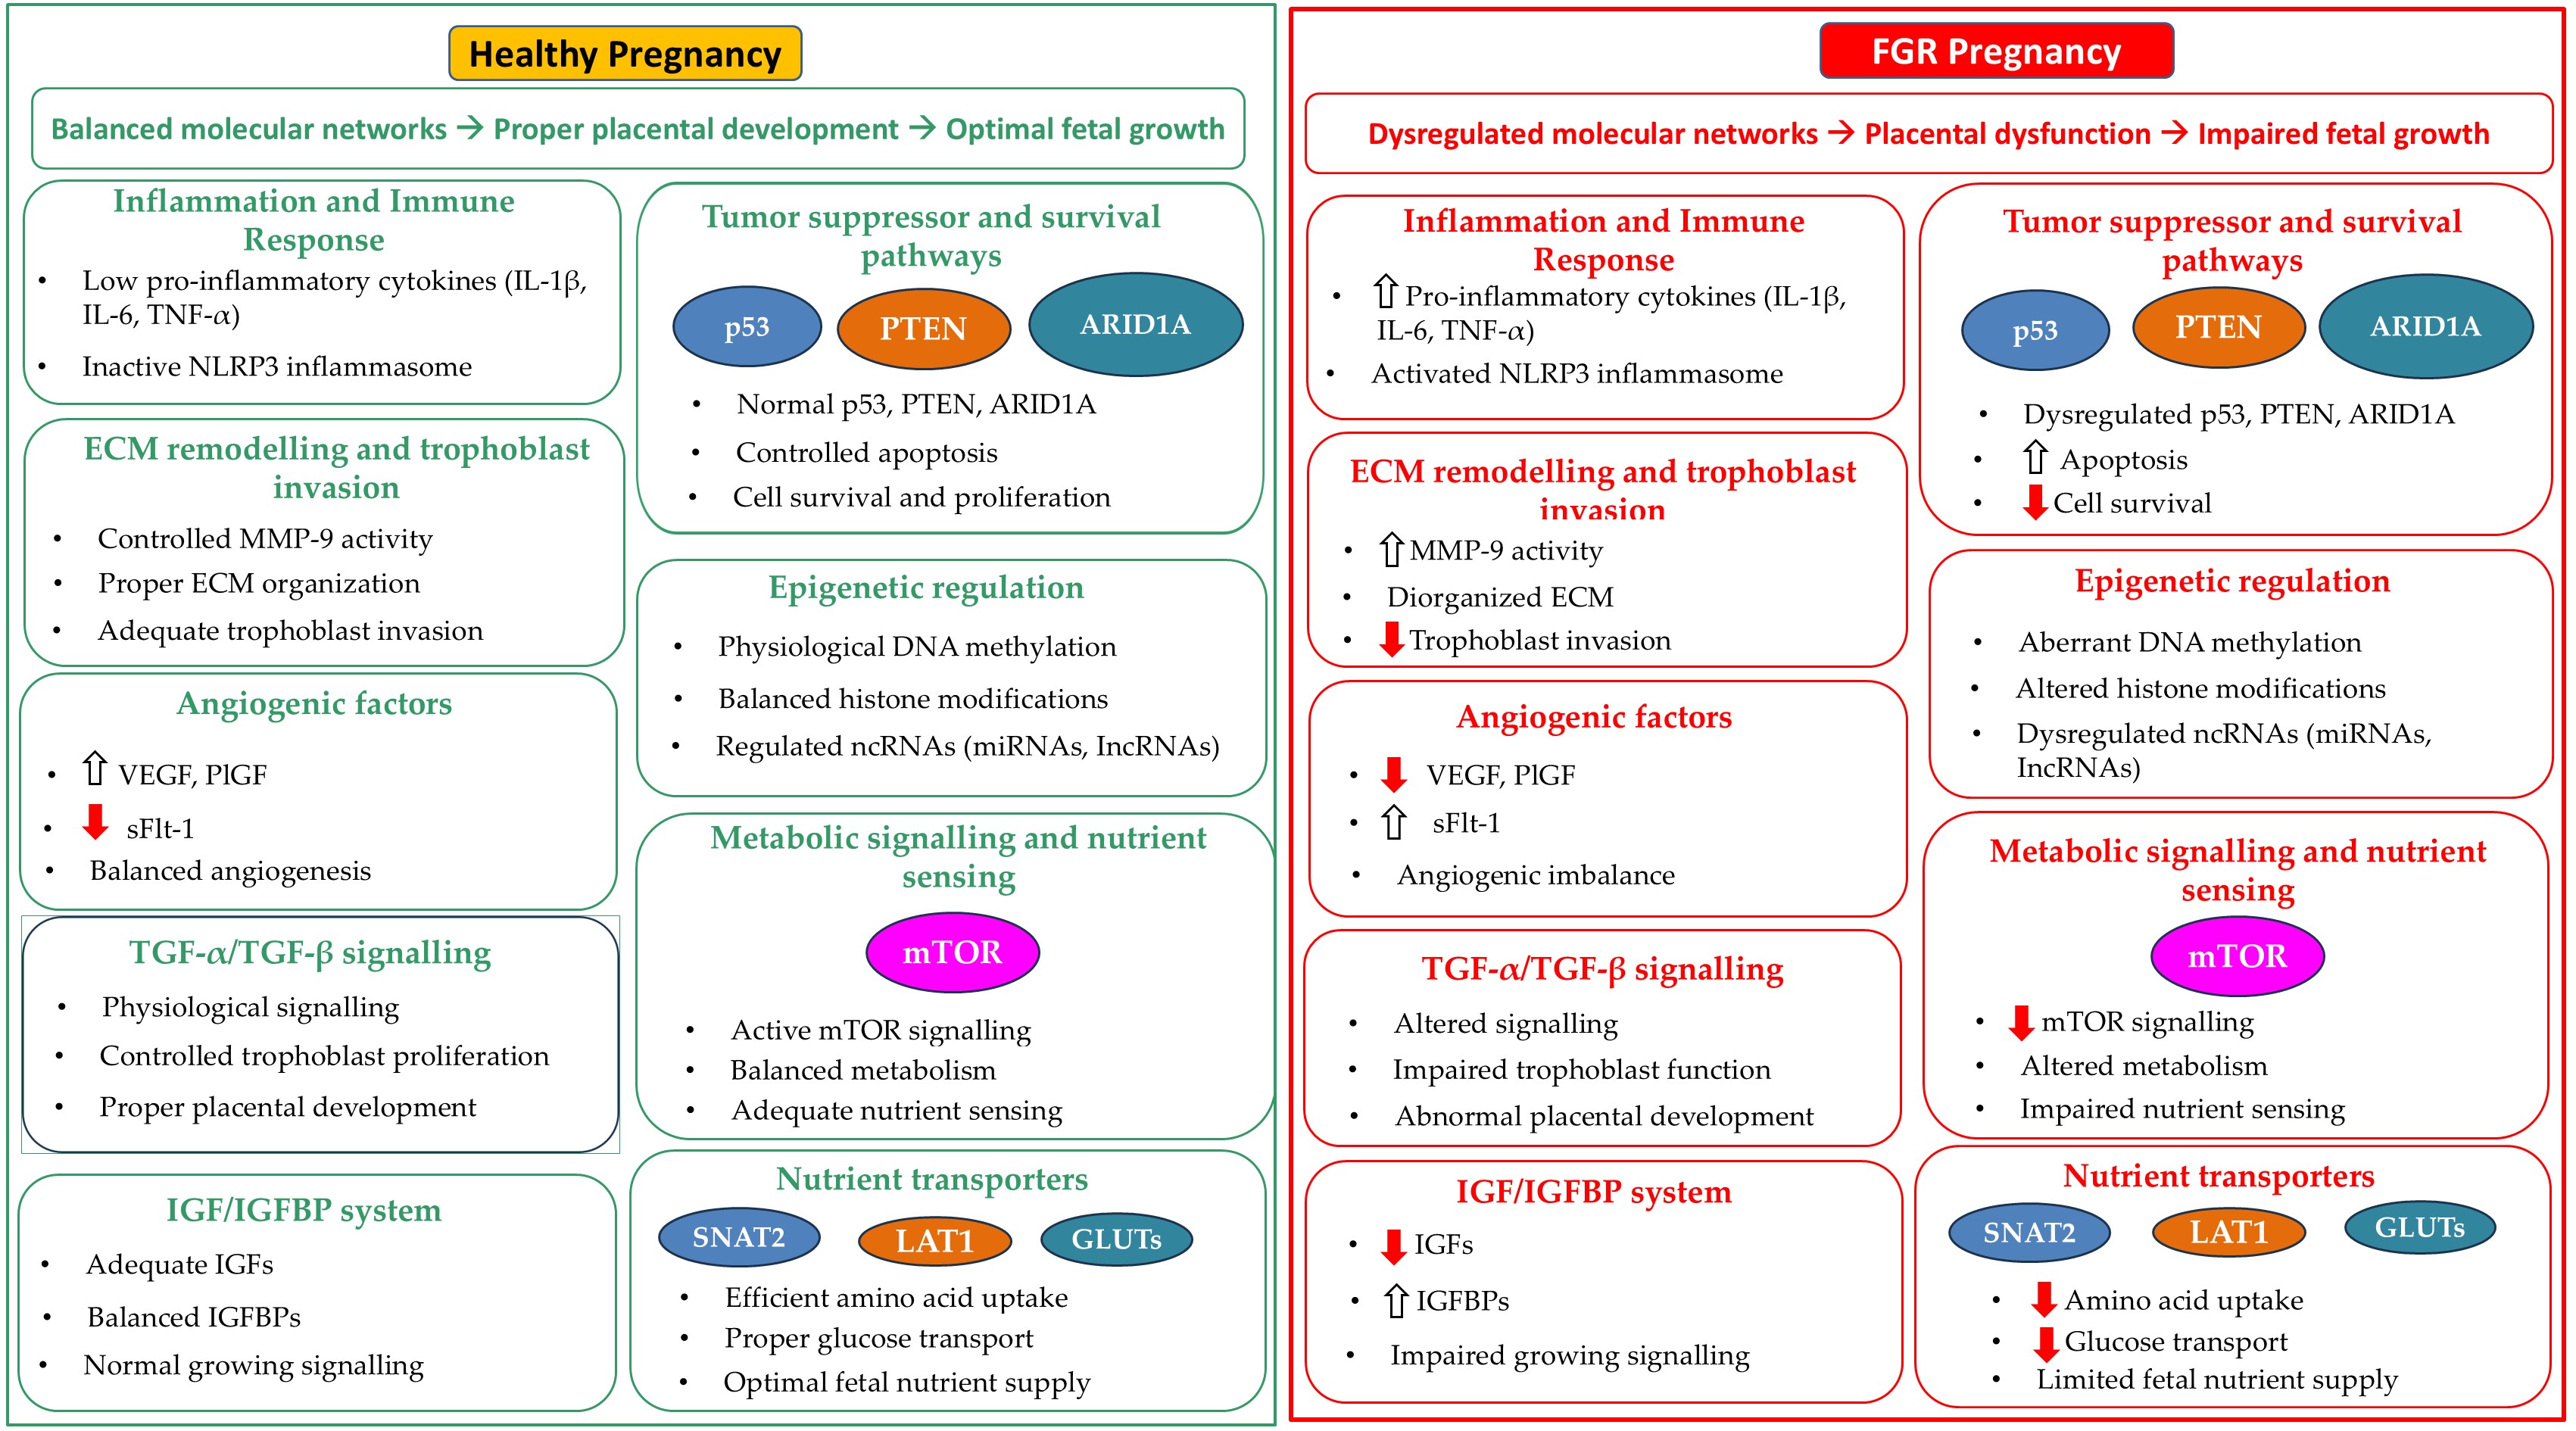
Placental development and structural homeostasis require strict, multidimensional coordination between intrinsic gene transcription networks, cell-cycle checkpoints, and cell survival signaling pathways at the maternal-fetal interface. While physiological early-stage placentation depends on the synchronized invasion of extravillous trophoblasts (EVTs) and rapid villous tissue proliferation, the severe ischemic and hypoxic stress conditions characterizing pathological placental insufficiency can permanently disrupt this biological equilibrium. At the direct core of this structural breakdown lies a sophisticated regulatory cross-talk handled by coordinated tumor suppressor pathways and upstream chromatin-regulatory mechanisms. As systematically illustrated in Figure 7, the orchestration of healthy placental development is tightly governed by two primary intrinsic molecular axes: tumor suppressor genes, including p53, PTEN, and ARID1A, acting as master cellular quality-control hubs; and detailed epigenetic modifications, encompassing global DNA methylation patterns, post-translational histone modifications, ATP-dependent chromatin remodeling complex dynamics, and non-coding RNA networks.
When these protective molecular pathways are compromised, the cellular architecture of the placenta undergoes profound, self-reinforcing pathological modifications. Instead of maintaining standard tissue turnover, aberrant signaling shifts trophoblast differentiation pathways toward structural decay, chronic cell-cycle arrest, and accelerated cellular senescence. The systemic consequences of this macromolecular disruption quickly cascade downwards, causing direct, severe downstream impacts on the developing fetal compartment. As carefully mapped out in the functional hierarchy of Figure 7, the cumulative execution of tumor suppressor hyperactivation and epigenomic closed-state silencing precipitates a unified pathogenic phenotype. This network breakdown is clinically manifested through impaired EVT invasion, defective spiral artery remodeling, and a profound angiogenic mismatch characterized by reduced VEGF/PlGF signaling and elevated anti-angiogenic sFlt-1 production. On a cellular level, this drives p53-mediated cell death, a total loss of PI3K/Akt survival signaling, and the physical down-regulation and trafficking failure of high-affinity glucose and essential amino acid transport systems, specifically GLUT1, SNAT2, and LAT1. Consequently, this multi-layered molecular loop induces systemic placental vascular dysfunction, cutting off the critical nutritional and oxygen supply lines required for normal embryogenesis and ultimately restricting the biological growth potential of the fetus.
5.1. The Role of the p53 Pathway in Trophoblast Apoptosis and FGR
The tumor suppressor p53 is a central regulator of cell-cycle arrest, DNA repair, apoptosis and senescence. During normal placental development, tightly controlled p53 activity helps maintain trophoblast homeostasis by balancing proliferation with removal of damaged or excess cells [120,121].
In pregnancies complicated by FGR, cellular stress may induce p53 activation, thereby promoting trophoblast apoptosis and contributing to placental dysfunction [121,122]. Research data have demonstrated increased p53 expression and activation in placentas from FGR pregnancies, particularly within the trophoblast compartment, while experimental evidence further implicates p53 signaling in trophoblast differentiation and placental vascular abnormalities [121]. Increased p53 activity can induce cell-cycle arrest and restrict trophoblast proliferation, while also activating pro-apoptotic pathways that promote trophoblast cell death [123,124,125]. Excessive loss of trophoblast cells may reduce the functional surface of the placenta and negatively affect trophoblast renewal and differentiation [56]. In parallel, dysregulated p53 activity may contribute to impaired placental vascular development and angiogenesis, potentially exacerbating the reduced vascular network characteristic of FGR and limiting the capacity of the placenta to meet the increasing oxygen and nutrient demands of the developing fetus [56]. p53 signaling may also respond to inflammatory and cellular stress associated with placental insufficiency. Placental dysfunction can promote p53 activation, cell-cycle arrest and apoptosis, providing a potential explanation for increased trophoblast cell death in FGR [121].
Overall, p53 appears to be an important regulator of trophoblast fate in FGR. Dysregulated p53 signaling may promote cell-cycle arrest, apoptosis and senescence while also influencing placental vascular development. These observations support further investigation of p53-related pathways as markers of placental dysfunction, although their clinical utility remains uncertain.
5.2. PTEN-Dependent Regulation of Placental Cell Survival and Angiogenic Signaling in FGR
Phosphatase and Tensin Homolog (PTEN) is a lipid phosphatase that acts as a major negative regulator of the phosphoinositide 3-kinase/protein kinase B (PI3K/AKT) signaling pathway. By dephosphorylating phosphatidylinositol-3,4,5-trisphosphate (PIP3) to phosphatidylinositol-4,5-bisphosphate (PIP2), PTEN limits PIP3-dependent AKT activation and thereby modulates downstream cellular responses. In the placenta, PI3K/AKT signaling regulates fundamental processes essential for placental development and function, including trophoblast proliferation, survival, differentiation, metabolism, and vascularization. Notably, impaired PI3K/AKT signaling has been reported in FGR placentas, suggesting that dysregulation of this pathway may contribute to placental dysfunction and FGR [126,127]. In placental tissues, the balance between PI3K/AKT activation and PTEN-mediated inhibition is therefore important for maintaining trophoblast function and normal placental development. Experimental evidence indicates that PTEN contributes to the regulation of trophoblast invasion and placental vascular remodeling, while alterations in PI3K/AKT signaling have been associated with impaired placental function and fetal growth [126,127].
In pregnancies complicated by FGR, evidence suggests that dysregulation of the PTEN/PI3K/AKT axis may contribute to impaired placental function. However, direct evidence that PTEN expression is consistently increased in FGR placental tissue remains limited. Studies of FGR placentas have identified alterations in regulatory miRNAs targeting PTEN, consistent with enhanced PTEN-mediated inhibition of PI3K/AKT signaling, while experimental studies demonstrate that PTEN can regulate trophoblast migration and invasion and influence placental and uterine vascular remodeling [126,128]. In addition, reduced PI3K and AKT phosphorylation has been demonstrated in human FGR placentas, providing evidence of impaired pathway activity in FGR [127]. Thus, dysregulation of PTEN or other components of the PI3K/AKT pathway may impair trophoblast proliferation, migration, survival, and vascular development, potentially contributing to placental insufficiency FGR.
Inflammatory signaling may also influence PTEN/PI3K/AKT activity in trophoblasts. Experimental activation of inflammatory pathways has been shown to alter PTEN expression and trophoblast invasion, suggesting that PTEN may act as a signaling node connecting inflammatory cues with placental cell behavior [130]. Whether this mechanism is directly involved in human FGR remains to be determined and requires further study.
Overall, PTEN is an important regulator of placental development through its control of PI3K/AKT signaling. Although consistent alteration of PTEN itself has not been established in human FGR, changes in the PTEN/PI3K/AKT axis may affect trophoblast proliferation, migration, invasion, survival and vascular development. Further studies should clarify which components of this pathway are altered in specific FGR phenotypes and whether they have biomarker or therapeutic relevance.
5.3. ARID1A Regulation of Trophoblast Differentiation and Placental Function in FGR
AT-rich interactive domain-containing protein 1A (ARID1A) is a core regulatory subunit of the SWI/SNF (Switch/Sucrose Non-Fermentable) chromatin-remodeling complex and contributes to the regulation of chromatin accessibility and transcriptional activity. Through this epigenetic function, ARID1A participates in cellular differentiation, proliferation, survival, and adaptation to cellular stress, processes that are particularly relevant to placental development and trophoblast function. In the human placenta, ARID1A is expressed in trophoblast populations and displays a distinct spatial pattern during normal placental development. Fantone et al. (2020) demonstrated that ARID1A is predominantly expressed in villous and extravillous cytotrophoblasts in normal placenta, whereas its expression is limited in the syncytiotrophoblast [130]. In placentas from pregnancies complicated by preeclampsia and intrauterine growth restriction (IUGR), however, ARID1A expression was also detected in the syncytiotrophoblast and syncytial knots, leading the authors to suggest that increased ARID1A expression in these compartments may be associated with impaired trophoblast differentiation [130].
The potential functional relevance of ARID1A to trophoblast biology is further supported by experimental evidence showing that ARID1A regulates trophoblast cell behaviour. In human trophoblast-like JEG-3 cells, ARID1A has been shown to modulate cell migration and invasion, with ARID1A overexpression suppressing both processes, whereas ARID1A knockdown enhanced them. These effects were associated with the regulation of Snail transcription and MMP-9 protein stability, indicating that ARID1A can influence cellular mechanisms involved in trophoblast motility and invasion [131]. Although these functional experiments were not performed specifically in FGR, they provide a biological rationale for considering altered ARID1A activity as a potential regulator of trophoblast behaviour in placental disorders.
Evidence directly linking ARID1A to FGR remains limited but is emerging. Altered ARID1A localization has been observed in placentas affected by FGR, particularly within the syncytiotrophoblast and syncytial knots, supporting an association between ARID1A dysregulation and abnormal trophoblast differentiation in growth-restricted pregnancies [130]. In late FGR, ARID1A expression may also vary within the placental vascular compartment in association with chronic placental insufficiency, suggesting that ARID1A could contribute to placental adaptation to vascular stress. However, the available evidence does not yet establish whether these alterations are causally involved in the pathogenesis of FGR or represent a placental response to chronic insufficiency. This distinction is important because FGR is characterized by complex abnormalities in placental development, including altered villous architecture and fetal vascular development [132].
ARID1A may also link placental chromatin regulation with cellular responses to adverse metabolic conditions. In placentas from pregnancies complicated by gestational diabetes, increased ARID1A expression has been observed, while ARID1A overexpression in trophoblast cells exposed to high glucose promoted cell-cycle arrest and cellular senescence. Mechanistically, ARID1A recruited GATA2 to the CDKN1A promoter, resulting in increased p21 expression and suppression of trophoblast proliferation [133]. Although these findings were obtained in the context of gestational diabetes rather than FGR, they provide experimental evidence that altered ARID1A activity may influence trophoblast homeostasis under conditions of metabolic stress [133]. Additional experimental findings indicate that ARID1A can regulate trophoblast homeostasis under adverse cellular conditions. In pregnancies complicated by gestational diabetes, increased placental ARID1A expression has been associated with trophoblast cell-cycle arrest and cellular senescence under high-glucose conditions. Mechanistically, ARID1A overexpression promotes the recruitment of GATA2 to the CDKN1A promoter, thereby increasing p21 expression and contributing to trophoblast dysfunction [133].
Taken together, current evidence supports a role for ARID1A in regulating trophoblast differentiation and cellular behaviour, while its specific contribution to FGR remains incompletely defined. In particular, further FGR-specific studies are required to determine whether altered ARID1A-dependent chromatin remodeling contributes directly to the transcriptional dysregulation, vascular abnormalities, and trophoblast dysfunction characteristic of placental insufficiency.
6. Epigenetic and Genomic Regulation of Placental Function: From Healthy Pregnancy to FGR
Epigenetic and genomic regulation constitute a fundamental layer of control over placental development, differentiation, and functional adaptation throughout pregnancy. The placental epigenome is established and dynamically modified during development, integrating developmental signals with maternal, nutritional, metabolic, and environmental influences. DNA methylation, histone modifications, ATP-dependent chromatin remodeling, genomic imprinting, and non-coding RNAs regulate the transcriptional programs required for trophoblast proliferation and differentiation, placental vascular development, nutrient transport, and endocrine function. Thus, epigenetic regulation should not be viewed exclusively as a pathological mechanism; rather, it is an essential component of normal placental development whose disruption may contribute to placental dysfunction and fetal growth restriction (FGR) [134,135,136].
In healthy pregnancy, epigenetic regulation permits cell-type-specific and gestational-age-dependent changes in gene expression while maintaining the functional plasticity of the placenta. Placental DNA methylation patterns differ from those of many somatic tissues, and both methylated and unmethylated genomic regions contribute to the regulation of trophoblast lineage specification and placental phenotype. Histone modifications and chromatin remodeling further determine the accessibility of regulatory DNA, whereas microRNAs (miRNAs) and other non-coding RNAs provide post-transcriptional control of gene networks. This multilayered regulation is particularly relevant to trophoblast invasion, differentiation, angiogenesis, and the capacity of the placenta to adapt to changing fetal and maternal demands [19,134].
Genomic imprinting represents a specialized epigenetic mechanism with particular relevance to placental biology. Imprinted genes are expressed according to parental origin and participate in the regulation of placental growth, morphology, and nutrient allocation. The IGF2/H19 locus is a well-characterized example. In normal development, the coordinated epigenetic regulation of this locus contributes to appropriate placental and fetal growth, while experimental disruption of placental Igf2 signaling can impair placental growth and subsequently fetal growth [102,135]. These observations support the concept that epigenetic regulation is integrated into the mechanisms by which the placenta matches its growth and transport capacity to fetal requirements.
6.1. DNA Methylation and Genomic Imprinting in Healthy Pregnancy and FGR
DNA methylation, predominantly occurring at CpG sites, is one of the principal mechanisms regulating gene transcription. In the placenta, methylation is developmentally dynamic and can influence promoters, enhancers, and other regulatory regions. During normal pregnancy, appropriate methylation patterns contribute to the establishment of trophoblast identity and the regulation of genes involved in placental growth, vascular development, endocrine activity, and nutrient exchange. Consequently, placental DNA methylation may reflect both intrinsic developmental programs and responses to the intrauterine environment [134,136].
Evidence from human placentas indicates that altered methylation of growth-related genes is associated with fetal growth phenotypes. Placental DNA methylation at IGF2, AHRR, HSD11B2, and WNT2 was associated with measures of fetal growth. Lower IGF2 methylation and higher HSD11B2 and WNT2 methylation were associated with increased odds of FGR. These findings support a relationship between placental DNA methylation and fetal growth; however, given the observational nature of such studies, they do not establish whether the observed methylation differences are causal, compensatory, or secondary to alterations in placental physiology [137].
Genome-wide approaches have extended these observations beyond individual candidate genes, providing evidence for broader epigenetic alterations in FGR. Differential DNA methylation has been reported in genomic regions involving genes and biological pathways related to angiogenesis, morphogenesis, immune regulation, and transcriptional control. Collectively, these findings suggest that altered DNA methylation may affect multiple biological processes involved in placental insufficiency rather than acting through a single growth-related gene. However, the interpretation of epigenome-wide associations in FGR should take into account differences in gestational age, placental cell composition, FGR phenotype, and analytical methodology, as these factors may contribute to variability between studies [138].
Genomic imprinting provides an additional mechanistic link between epigenetic regulation and fetal growth. Alterations in the H19/IGF2 region have been reported in placentas from growth-restricted pregnancies. Reduced IGF2 expression and loss of normal imprinting have been observed in a subset of FGR placentas. These findings suggest that dysregulation of imprinted genes may contribute to abnormal placental and fetal growth; however, the variability in reported methylation and imprinting patterns indicates that such abnormalities may not be consistently present across all FGR phenotypes [136,139].
6.2. Histone Modifications and Chromatin Remodeling in Placental Function
DNA methylation operates within a broader chromatin-regulatory system that includes post-translational histone modifications and ATP-dependent chromatin remodeling. Histone acetylation and methylation can modify chromatin accessibility and thereby influence the recruitment of transcriptional machinery. In the placenta, these mechanisms are relevant to the highly dynamic transitions between trophoblast proliferation, differentiation, invasion, and interaction with the maternal vasculature. Epigenetic regulation therefore provides a means by which developmental and environmental signals can be translated into changes in transcription without altering the underlying DNA sequence [19,134].
In FGR, changes in chromatin state have been investigated using genome-wide approaches, including chromatin accessibility and histone-mark profiling. Such studies support the presence of altered regulatory landscapes in growth-restricted placentas, with changes involving pathways related to hypoxia, angiogenesis, metabolism, and cellular differentiation [140]. Specifically, genome-wide mapping of active histone marks like H3K27ac has revealed widespread alterations in enhancer profiles near genes controlling microvascular expansion and tissue remodeling [141,142]. The biological significance of these findings is consistent with the concept that FGR is associated with coordinated changes in several placental regulatory systems rather than an isolated defect in a single signaling pathway [140]. Nevertheless, the direction and functional significance of individual histone changes may depend on placental cell type, gestational age, and the clinical subtype of FGR [139,141].
ATP-dependent chromatin remodeling complexes, including SWI/SNF-family complexes, provide another level of transcriptional regulation by altering nucleosome positioning and DNA accessibility [142]. Their potential importance in placental development is particularly relevant because trophoblast differentiation requires substantial and tightly regulated changes in gene expression [142,143]. Although direct evidence linking individual SWI/SNF components to human FGR remains more limited than the evidence for DNA methylation, integrated epigenomic studies increasingly indicate that altered chromatin accessibility can accompany changes in DNA methylation and transcription [1130,144]. These observations support further investigation of chromatin remodeling as a mechanistic component of placental dysfunction [144,145].
6.3. Non-Coding RNAs and Post-Transcriptional Regulation in Healthy Pregnancy and FGR
Non-coding RNAs constitute an additional regulatory layer connecting genomic activity with placental phenotype. miRNAs can bind target mRNAs and regulate their stability or translation, whereas long non-coding RNAs (lncRNAs) may act through interactions with RNA molecules, transcriptional regulators, or chromatin-associated proteins. During normal placental development, these mechanisms participate in trophoblast proliferation, differentiation, migration, and responses to growth-factor signaling. The functional effects of miR-377, let-7a, and miR-145 on trophoblast growth and insulin-like growth factor-related signaling demonstrate how post-transcriptional regulation can modulate placental responses to developmental and maternal signals [19,146].
In FGR, differential miRNA expression has been associated with pathways involved in angiogenesis and nutrient transport. Altered placental miRNA expression has been identified in term FGR pregnancies, with predicted target genes implicated in angiogenic pathways and amino-acid transport. These findings are relevant to placental insufficiency, as impaired vascular adaptation and reduced nutrient transfer are key features of many FGR phenotypes [147].
Selective FGR has also been associated with coordinated changes in placental miRNA networks. Differentially expressed miRNAs have been identified in placentas from monochorionic twin pregnancies complicated by selective IUGR, with pathway analyses implicating TGF-β, MAPK, and Wnt signaling [148]. Evidence also supports the involvement of lncRNA–miRNA interactions in the molecular regulation of selective FGR [148]. Reduced MALAT1 expression has been observed in placental tissue from the smaller twin, with evidence of a regulatory relationship involving the miR-424/ERRγ/HSD17B1 axis, linking non-coding RNA regulation to trophoblast and endothelial functions [149]. These findings highlight the potential role of non-coding RNAs in integrating angiogenic, proliferative, and metabolic signals within the placenta [148,149].
The imprinted lncRNA H19 provides an additional connection between genomic imprinting and post-transcriptional regulation. H19 is located within the imprinted H19/IGF2 domain and has been implicated in placental growth regulation. Lower H19 expression has been observed in SGA placentas compared with AGA placentas in late normotensive pregnancy, accompanied by a tendency toward reduced IGF2 and decorin expression. These observations suggest that altered non-coding RNA expression may occur even in growth-restricted pregnancies without major histopathological abnormalities, although the functional and causal significance of these associations requires further investigation [150].
6.4. Integrated Epigenomic Regulation and Implications for Placental Dysfunction in FGR
The available evidence supports an integrated model in which DNA methylation, genomic imprinting, histone modifications, chromatin accessibility, and non-coding RNAs interact to regulate placental function [19,134]. In normal pregnancy, these mechanisms permit coordinated adaptation of trophoblasts, placental vessels, and nutrient-transport systems to the changing requirements of the fetus [102,135]. In FGR, alterations in one regulatory layer may influence several others, potentially generating persistent changes in gene expression and cellular phenotype [138,147]. This framework is particularly relevant to pathways controlling angiogenesis, hypoxic adaptation, trophoblast differentiation, growth-factor signaling, inflammation, and nutrient transport [144,149].
Recent integrative methylome studies strengthen the concept that FGR-associated epigenetic signatures are distributed across biological pathways rather than restricted to a single locus [139]. Reproducible methylation differences have been identified in genes involved in vascular development, morphogenesis, immune regulation, and transcriptional control. In addition, multi-omics analyses of selective FGR integrating DNA methylation, chromatin accessibility, and transcriptomic data have revealed coordinated regulatory changes [138]. Such approaches may help distinguish primary molecular abnormalities from secondary consequences of placental hypoxia or altered cellular composition, although causal inference remains a major challenge [134,144].
From a translational perspective, placental epigenetic signatures may have potential value as biomarkers of placental dysfunction because DNA methylation and non-coding RNA patterns can reflect molecular states that precede or accompany clinical manifestations of FGR [52,134]. However, the use of epigenetic markers for prediction or diagnosis requires careful consideration of tissue specificity, gestational age, placental cell composition, maternal exposures, fetal sex, and the distinction between constitutional smallness and pathological growth restriction [135,139]. At present, the evidence supports continued investigation rather than routine clinical application of individual placental epigenetic markers [19,138].
Overall, epigenetic and genomic regulation should be regarded as a central component of the molecular landscape of placental function. The transition from normal pregnancy to FGR can be conceptualized not as a simple gain or loss of a single epigenetic mark, but as a disturbance of interconnected regulatory networks. Future studies combining methylome, chromatin-accessibility, transcriptomic, proteomic, and single-cell approaches may clarify which alterations are mechanistically involved in placental dysfunction and which represent adaptive or secondary responses. Such integrated analyses may ultimately support molecular stratification of FGR and the identification of placenta-specific targets for intervention.
7. Metabolic Signaling and Nutrient Transport in Placental Function: From Homeostasis to FGR
Placental metabolism is a dynamic interface between maternal nutrient availability and fetal growth. Rather than functioning as a passive conduit, the placenta senses oxygen, nutrients, hormones, and inflammatory signals and adjusts cellular metabolism, growth, and transplacental substrate transfer accordingly. This adaptive capacity is particularly important because fetal growth depends not only on the amount of substrate reaching the maternal–fetal interface but also on the ability of trophoblast cells to sense, metabolize, and selectively transport that substrate. Insulin/IGF signaling, PI3K/AKT, mechanistic target of rapamycin (mTOR), AMP-activated protein kinase (AMPK), and related nutrient-sensing pathways therefore form an interconnected regulatory system linking placental growth with nutrient transport [20,135].
In healthy pregnancy, this metabolic network permits the placenta to adapt progressively to the increasing demands of the fetus. mTOR signaling integrates amino-acid and energy availability with trophoblast protein synthesis and transporter activity, while insulin and IGF signaling provide additional endocrine inputs. Nutrient transporters, in turn, influence intracellular amino-acid and glucose availability and thereby feed back into metabolic signaling. The resulting system is better understood as a regulated circuit than as a collection of independent transport proteins. This network perspective is important for FGR because abnormalities in one component may propagate to other functional domains, including trophoblast growth, vascular adaptation, mitochondrial metabolism, and inflammatory signaling [21,117].
Evidence from human and experimental studies indicates that placental nutrient transport is altered in FGR. Reduced activity of amino-acid transport systems, changes in transporter abundance or localization, and disturbances in nutrient-sensing pathways have all been reported. Importantly, these abnormalities do not necessarily have identical magnitude or direction in every FGR pregnancy. Differences in gestational age, severity, fetal phenotype, maternal disease, placental cell composition, and the distinction between early- and late-onset FGR may contribute to this heterogeneity. Accordingly, the most informative interpretation is not that FGR is characterized by a single “defective transporter”, but that placental nutrient acquisition and utilization may become uncoupled from fetal growth requirements [20,56,117].
7.1. mTOR and Nutrient-Sensing Pathways in Placental Homeostasis and FGR
The mTOR pathway is a central integrator of cellular nutrient and growth signals. In the placenta, mTORC1 and mTORC2 connect amino-acid availability, insulin/IGF signaling, cellular energy status, and protein synthesis with the regulation of nutrient transport. Placental mTOR signaling has been shown to be associated with amino-acid transporter activity and fetal growth, providing a mechanistic link between nutrient sensing and transplacental nutrient supply. The significance of this pathway extends beyond nutrient transport, as mTOR also influences trophoblast growth, differentiation, and metabolic adaptation [21,151].
In FGR, placental mTOR signaling is generally reduced, although the molecular phenotype may vary between clinical subtypes. Altered placental mTOR signaling has been reported in human FGR, while impaired mTOR activity has also been associated with reduced amino-acid transport. In this context, decreased mTOR activity may represent both a marker of placental nutrient stress and a potential mechanism contributing to insufficient nutrient transport capacity. This reciprocal relationship provides an important conceptual link between metabolic stress and placental insufficiency, rather than considering them as independent abnormalities [152].
The mTOR network also interacts with oxygen sensing and cellular stress. Nutrient deprivation, hypoxia, and oxidative or endoplasmic-reticulum stress can converge on nutrient-sensing pathways, potentially reducing anabolic activity at precisely the time when the placenta must maintain or increase its transport capacity. This integration is consistent with the broader molecular model of FGR in which vascular insufficiency, oxidative stress, inflammation, and metabolic dysfunction reinforce one another rather than occurring as isolated events [56].
7.2. System A Amino-Acid Transport and SNAT2
System A is a sodium-dependent amino-acid transport system that transfers small neutral amino acids, including glutamine, alanine, and serine, into trophoblast cells. SNAT2 (SLC38A2) is one of its principal transporters. System A is important not only because it contributes directly to the supply of amino acids to the fetal compartment, but also because intracellular amino-acid availability regulates trophoblast protein synthesis, cellular volume, and nutrient-sensing pathways. Thus, transporter activity links extracellular nutrient availability to intracellular metabolic state [20,153].
Reduced System A activity has been demonstrated in placental microvillous membrane preparations from pregnancies complicated by IUGR, providing direct functional evidence of impaired placental amino-acid transport [154]. Importantly, the magnitude of this reduction appears to be associated with the severity of fetal compromise, with particularly marked decreases reported in pregnancies with reduced umbilical blood flow [154,155,156]. Altered expression of the System A transporter SNAT2 has also been reported in IUGR placentas, with lower SNAT2 mRNA levels observed in pregnancies associated with reduced umbilical blood flow [157]. Together, these findings suggest that impaired System A-mediated amino-acid transport may be related not only to restricted fetal growth but also to the severity of underlying placental vascular dysfunction.
A critical point for interpretation is that transporter abundance does not necessarily reflect transporter function. SNAT2 activity depends not only on its overall expression but also on its trafficking to and retention within the trophoblast plasma membrane, processes regulated by mTOR signaling, ubiquitination, and cytoskeletal mechanisms. Consequently, measurements of transporter mRNA or total protein abundance alone may not fully capture functional impairment in placental amino-acid transport. This distinction supports a network-based interpretation of FGR, in which impaired nutrient transfer may arise from altered signaling, post-translational regulation, and transporter trafficking even when changes in total transcript or protein abundance are relatively modest [158,159,160].
The interaction between SNAT2 and mTOR signaling is particularly relevant to placental nutrient sensing. Amino acids transported through System A can contribute to intracellular amino-acid sensing and mTORC1 activation, while mTOR signaling regulates the activity and plasma-membrane trafficking of key amino-acid transporters, including SNAT2. In FGR, impaired mTOR signaling has been associated with reduced SNAT2 trafficking and System A activity, potentially limiting amino-acid availability to both the fetus and trophoblast cells. This bidirectional relationship provides a mechanistic framework in which disturbances in nutrient transport and intracellular nutrient signaling may reinforce one another, contributing to persistent metabolic dysfunction in placental insufficiency [152,158,161,162,163].
7.3. System L, LAT1, and Essential Amino-Acid Availability
System L provides a complementary transport route for large neutral amino acids, including essential amino acids such as leucine. LAT1 (SLC7A5) is a major System L transporter in trophoblasts. Unlike System A, System L operates largely as an exchanger and depends on the intracellular amino-acid pool. This functional relationship means that disturbances in one transport system can influence the performance of another, reinforcing the concept that placental nutrient transport is an integrated network [153].
Leucine is particularly important because it is both a substrate and a metabolic signal capable of influencing anabolic pathways, including mTORC1. Consequently, LAT1 occupies a strategic position at the interface of amino-acid transfer and trophoblast growth. Relationships between placental mTOR signaling and System L amino-acid transport have been demonstrated, supporting the interpretation that nutrient transport and intracellular signaling are mechanistically interconnected [21,151].
In FGR, placental amino-acid transport capacity is substantially reduced, with abnormalities reported across multiple transport systems, including System L [156]. Impaired nutrient transport is considered an important component of FGR pathophysiology, as altered transporter activity may limit the delivery of essential substrates to the fetus [56]. Importantly, these findings suggest that placental nutrient insufficiency reflects a broader disruption of coordinated nutrient-handling mechanisms rather than an isolated defect in a single transporter such as LAT1 [164].
7.4. Glucose Transport and Placental Metabolic Adaptation
Glucose is an essential substrate for both placental and fetal metabolism. GLUT1 (SLC2A1) is the predominant glucose transporter in human placental trophoblasts, while GLUT3 and other GLUT isoforms may contribute according to cellular context and metabolic demand. Placental glucose transfer is influenced by maternal glucose concentration, placental metabolism, oxygen availability, and fetal requirements, making glucose transport part of a broader adaptive system rather than a fixed process [20].
The relationship between placental glucose transport and FGR is more complex than a simple reduction in GLUT expression. Placental glucose uptake and utilization are influenced by maternal substrate availability, insulin signaling, oxygenation, and the metabolic demands of the placenta and fetus [165,166]. In addition, fetal glucose concentrations reflect not only placental glucose transfer but also fetal metabolic adaptation and glucose utilization [167]. Consequently, differences in GLUT expression should not automatically be interpreted as direct evidence of reduced transplacental glucose flux, particularly because the functional contribution of individual GLUT isoforms depends on their cellular localization and membrane distribution [166,168]. This distinction is important when integrating metabolic findings across different FGR phenotypes.
In some growth-restricted pregnancies, impaired placental perfusion and hypoxic or oxidative stress may alter glucose uptake and utilization without producing uniform changes in GLUT abundance [165,166]. Conversely, compensatory alterations in GLUT expression may occur in response to changes in maternal glucose availability or oxygenation. For example, increased placental GLUT3 expression has been reported in late-onset IUGR, suggesting that transporter regulation may represent an adaptive response to altered placental conditions rather than simply a marker of impaired transport [169]. The interpretation of GLUT biology therefore benefits from integrating transporter expression with functional glucose-transport measurements, placental glucose metabolism, maternal–fetal glucose concentration gradients, and clinical indicators of placental insufficiency [166].
7.5. Integration of Nutrient Transport with Oxygen, Inflammation, and Oxidative Stress
Nutrient transport cannot be separated from placental oxygenation and vascular function. The developing placenta normally experiences changing oxygen conditions, and physiological redox signaling participates in trophoblast differentiation and angiogenesis. When placental perfusion becomes inadequate, repeated hypoxia–reoxygenation can increase oxidative and nitrative stress, impair mitochondrial function, and alter trophoblast survival. Placental oxidative and nitrative stress in FGR may impair nutrient transfer while promoting trophoblast dysfunction, cellular senescence, and cell death. Thus, impaired nutrient transport may represent not only a consequence of placental vascular dysfunction but also a mechanism through which oxidative and metabolic stress further compromise placental function [170].
Inflammatory signaling provides another connection between metabolic and structural dysfunction. Cytokines and inflammatory mediators can modify trophoblast metabolism and transporter activity, while metabolic stress can itself activate inflammatory pathways. This reciprocal interaction is consistent with the broader concept of FGR as a network disorder involving angiogenic imbalance, inflammation, oxidative stress, and nutrient transport rather than a single pathogenic cascade [56].
The resulting model can be summarized as a functional loop: impaired placental perfusion reduces oxygen and nutrient availability; cellular stress and redox imbalance alter trophoblast metabolism and nutrient sensing; mTOR and related pathways become dysregulated; transporter trafficking or activity is impaired; and reduced nutrient transfer further limits the resources available to the placenta and fetus. This formulation provides a mechanistic bridge between the vascular abnormalities discussed in earlier sections and the epigenetic and genomic regulation.
7.6. From Metabolic Signatures to Biomarker Development
The integrated metabolic model also has important implications for biomarker development. A single nutrient transporter is unlikely to capture the full biological heterogeneity of FGR, because placental nutrient transport is regulated not only by transporter abundance but also by upstream signaling pathways, oxygen and nutrient availability, cellular stress, and placental function [6,171,172]. In FGR, alterations in mTOR and other nutrient-sensing pathways, together with impaired amino-acid and glucose transport, occur in the context of abnormal placental perfusion and trophoblast dysfunction, supporting a multidimensional rather than single-marker approach [6,172]. A more informative strategy would therefore combine metabolic indicators with angiogenic markers such as placental growth factor (PlGF) and soluble fms-like tyrosine kinase-1 (sFlt-1), inflammatory markers, epigenetic signatures, and trophoblast- or placenta-derived extracellular vesicles, and interpret these molecular measurements alongside ultrasound and Doppler findings [12,173]. Evidence that sFlt-1/PlGF measurements may provide additional information when combined with ultrasound parameters further supports this integrative concept, although the clinical utility of multimarker strategies in FGR remains under investigation and requires prospective validation [57].
The potential value of multimodal profiling is supported by the increasing use of multi-omics approaches to characterize FGR placentas. Recent work emphasizes that FGR encompasses several interacting molecular programs, including impaired trophoblast invasion, angiogenic imbalance, oxidative stress, nutrient-transport failure, and epigenetic remodeling. Such findings support the development of molecularly stratified phenotypes, but they do not yet establish that any individual metabolic signature is sufficiently validated for routine clinical prediction [56,174].
From this perspective, the most original and clinically relevant contribution of metabolic research may not be the identification of another isolated transporter abnormality, but the integration of transporter activity with the upstream signaling state of the placenta. Longitudinal studies combining maternal circulating biomarkers, placental molecular profiling, functional transport measurements, and Doppler phenotyping may help determine whether metabolic abnormalities precede clinically detectable FGR or mainly represent downstream consequences of established placental insufficiency.
8. Discussion
The molecular landscape of FGR presented in this review shifts the pathophysiological paradigm from single-pathway abnormalities to an integrated, multidimensional network operating at the maternal–placental–fetal interface. The structural and functional failures characterising placental insufficiency do not arise from isolated genetic or environmental insults; rather, they represent a coordinated cascade where immunologic, angiogenic, growth-regulatory, epigenetic, and metabolic pathways continuously reinforce one another. Understanding how these systems converge is essential for transitioning from purely observational clinical surveillance to targeted, mechanism-based therapeutic strategies [56,175]. A comprehensive matrix summarizing these distinct molecular factors, their physiological roles, and their specific structural contributions to FGR pathogenesis is provided in Table 1.
A central axis of this disease process is the pro-inflammatory shift within the uterine-placental-fetal immune environment. While healthy pregnancy demands a delicate anti-inflammatory equilibrium mediated by cytokine pathways such as IL-10 to prevent maternal rejection and maintain endothelial stability, FGR pregnancies display a pronounced baseline inflammation (Table 1) [27,28]. The concurrent elevation of classical pro-inflammatory cytokines (such as TNF-α, IL-1β, and IL-6) and dysregulated adipokines promotes a state of chronic placental oxidative stress [31,176]. This hostile microenvironment directly compromises trophoblast health. As shown in the cumulative data, the hyperactivation of the intracellular NLRP3 inflammasome further amplifies this damage, driving gasdermin-D-dependent pyroptosis (Table 1) [9,43,45]. The resulting loss of viable trophoblast cells limits the structural expansion of the placenta and impairs its tissue remodeling capacity [46,177].
This inflammatory signaling functionally intersects with extracellular matrix (ECM) turnover and vascular adaptation, predominantly through the dysregulation of matrix metalloproteinases. Under physiological conditions, MMP-9 facilitates the degradation of basement membranes to allow the invasion of extravillous trophoblasts into maternal spiral arteries—a prerequisite for establishing low-resistance uteroplacental blood flow [49,178]. In FGR, the persistent activation of stress-responsive transcription factors, such as NF-κB and HIF-1α, alters the proteolytic equilibrium by shifting the balance between MMP-9 and its tissue inhibitors (TIMPs) (Table 1) [179,180]. The consequence is incomplete vascular remodeling, which leaves the placenta vulnerable to intermittent perfusion, hypoxia, and ischemia-reperfusion injuries [50,58].
Furthermore, this hemodynamic failure feeds directly into the angiogenic imbalance that defines the clinical presentation of placental FGR. The severe reduction of free pro-angiogenic factors (VEGF and PlGF) is exacerbated by the overproduction of sFlt-1, which acts as a circulating decoy receptor (Table 1) [72,74]. The sFlt-1/PlGF ratio has emerged as a cornerstone circulating biomarker capable of distinguishing pathological FGR from constitutional fetal smallness [117,181]. However, as synthesized in this review, angiogenic factors are not merely vascular signaling molecules; they possess autocrine and paracrine actions that dictate trophoblast proliferation, differentiation, and metabolic viability [62,69]. For instance, lower PlGF signaling impairs the production of cytoprotective proteins like XIAP, rendering the trophoblast layer highly susceptible to intrinsic, caspase-dependent apoptotic pathways (Table 1) [182,183]. The downstream manifestation of this compromised placental architecture is the failure of nutrient transport, a process governed by growth factor networks and metabolic sensors. Fetal growth is strictly limited by the transport capacity of the placenta for glucose and essential amino acids [20,184]. Crucial amino acid exchange systems, represented by the sodium-dependent System A transporter SNAT2 and the essential amino acid exchanger LAT1, exhibit markedly reduced activity and altered plasma membrane trafficking in FGR placentas (Table 1) [156,185]. This transport breakdown is directly linked to the inhibition of the mechanistic target of rapamycin (mTOR) signaling pathway, a central intracellular nutrient sensor (Table 1) [21]. Hypoxia and localized nutrient deprivation suppress mTOR phosphorylation, thereby downregulating transporter expression and restricting protein synthesis within both the placenta and the fetus [186,187]. This metabolic constraint is further compounded by alterations in the high-affinity glucose transporters GLUT1 and GLUT3, as well as the insulin-responsive GLUT4, which reflect a state of severe local metabolic stress [185,188].
Crucially, this entire metabolic and structural phenotype is orchestrated by an underlying layer of epigenetic and genomic dysregulation. The placenta exhibits a highly dynamic epigenome that translates maternal and environmental stress into stable, long-term alterations in gene transcription [19,134]. Aberrant DNA methylation patterns across the placental genome, particularly within promoter regions of growth-related loci such as IGF2, HSD11B2, and WNT2, directly correlate with reduced birth weight and placental insufficiency (Table 1) [137,189]. Disruptions in genomic imprinting, such as the loss of normal paternal expression at the H19/IGF2 locus, strip the placenta of key mitogenic signals required for matching microvascular expansion to fetal demand [139,190]. These methylome changes operate alongside distinct histone modifications (such as altered H3K27ac patterns) and downregulations in global chromatin accessibility mediated by complexes like SWI/SNF and its ARID1A subunit (Table 1) [140,191]. When these chromatin-regulatory mechanisms are disrupted, cell fate pathways are skewed toward cell-cycle arrest, senescence, and apoptosis via the overactivation of tumor suppressors like p53 or the loss of survival hubs like the PTEN/PI3K/AKT axis [122,126,192]. Finally, the post-transcriptional layer managed by non-coding RNAs provides a rapid, systemic amplification of these defects. Specific microRNAs (such as miR-424, miR-15b, and miR-146a) and long non-coding RNAs (such as H19 and MALAT1) form complex regulatory circuits that simultaneously repress multiple target transcripts controlling angiogenesis, amino acid transport, and chronic inflammatory resolution (Table 1) [147,150,193].
Taken together, these interconnected molecular networks may inform the development of multidimensional biomarker strategies and future mechanism-based therapeutic interventions in FGR. Rather than relying on a single molecular marker, integration of angiogenic biomarkers such as sFlt-1/PlGF with circulating microRNAs, placental epigenetic signatures, extracellular vesicles, and other molecular readouts may improve biological characterization and molecular stratification of FGR phenotypes [12,14,191,194]. In parallel, identification of dominant pathological pathways may support the development of targeted interventions, including placenta-directed gene therapy and selective modulation of inflammatory or trophoblast regulatory pathways, although these approaches remain experimental and require rigorous validation of maternal and fetal safety [9,195]. Thus, integration of longitudinal molecular profiling with established clinical parameters such as ultrasound and Doppler assessment may represent an important step toward biomarker-guided, mechanism-based management of FGR.
From a clinical perspective, identifying these interconnected mechanisms underlines the limitations of traditional, single-agent therapies. Historical trials evaluating non-specific treatments, such as sildenafil or general antioxidant supplementation, have often yielded heterogeneous or disappointing results because they target isolated clinical symptoms rather than the root regulatory network [196,197]. Future progress depends on the molecular stratification of FGR phenotypes, differentiating early-onset, severe vascular diseases from late-onset, metabolic insufficiencies [198,199]. Emerging preclinical strategies—including selective NLRP3 inflammasome inhibitors, targeted delivery of growth factor genes, microRNA-based therapeutics, and mesenchymal stem cell-derived extracellular vesicles—represent promising approaches for restoring placental homeostasis and potentially improving placental function (Table 1) [9,200]. However, translating these experimental interventions into safe clinical practices demands a meticulous evaluation of cell specificity, maternal systemic effects, and long-term fetal developmental toxicity. Until multi-omics longitudinal biomarker profiling is fully integrated with functional human models, the primary management of FGR will remain centered on precise clinical surveillance and the optimization of delivery timing [202,203].
Taken together, the evidence discussed above supports a network-based model of placental dysfunction in FGR, in which inflammatory, vascular, metabolic, cellular-survival, and epigenetic abnormalities are functionally interconnected rather than operating as isolated pathways. The convergence of these mechanisms ultimately compromises trophoblast integrity, uteroplacental vascular adaptation, nutrient sensing and transport, and placental capacity to support fetal growth. Figure 8 summarizes this integrated molecular framework and highlights the transition from upstream placental stress signals to downstream functional consequences, while also linking molecular characterization with emerging biomarker and therapeutic strategies.
8.1. Translational Implications for Biomarker Development and Mechanism-Based Therapeutic Interventions
The integrated molecular framework presented in this review shifts the pathophysiological paradigm from single-pathway abnormalities to an integrated, multidimensional network operating at the maternal–placental–fetal interface. The structural and functional failures characterising placental insufficiency do not arise from isolated genetic or environmental insults; rather, they represent a coordinated cascade where immunologic, angiogenic, growth-regulatory, epigenetic, and metabolic pathways continuously reinforce one another. Understanding how these systems converge is essential for transitioning from purely observational clinical surveillance to targeted, mechanism-based therapeutic strategies [5,56].
One of the most immediate translational opportunities lies in the expansion of circulating biomarker panels. The angiogenic imbalance represented by increased sFlt-1 and reduced PlGF, and particularly the maternal sFlt-1/PlGF ratio, has already demonstrated substantial clinical potential for identifying placental insufficiency and differentiating pathological FGR from constitutional smallness [12,14,118,181]. However, angiogenic biomarkers primarily capture one component of placental dysfunction and may not adequately reflect the inflammatory, epigenetic, metabolic, and trophoblast-specific abnormalities described in this review. Consequently, future biomarker development may benefit from combining circulating angiogenic factors with inflammatory mediators, placental-derived microRNAs, cell-free nucleic acids, and molecular signatures related to trophoblast function and nutrient transport.
Placental DNA methylation profiles have already been associated with fetal growth phenotypes, providing proof-of-principle that epigenetic signatures may capture clinically relevant alterations in placental biology [18,137]. Similarly, systematic evidence indicates that specific placental and circulating miRNA profiles are associated with FGR and regulate pathways involved in angiogenesis and PI3K/AKT signaling, although their clinical utility requires validation in longitudinal maternal blood samples and well-characterized FGR populations [147,194]. More recently, integrative analyses combining chromatin accessibility, DNA methylation, and transcriptomic data have demonstrated coordinated epigenetic and transcriptional alterations in FGR placentas, supporting the concept that multi-omics signatures may provide a more comprehensive representation of disease biology than individual biomarkers [191]. Thus, the future biomarker framework should move toward longitudinal, multimodal panels integrating circulating molecular signals with ultrasound and Doppler parameters, allowing molecular stratification of FGR phenotypes and potentially improving the distinction between predominantly vascular, inflammatory, and metabolic forms of placental dysfunction.
The same network-based concept has direct implications for therapeutic development. Rather than targeting a single downstream consequence of placental insufficiency, mechanism-based interventions could be designed to restore specific dysfunctional molecular nodes according to the biological phenotype of each pregnancy. Experimental evidence supporting increased placental NLRP3 signaling in FGR provides a rationale for investigating selective inflammasome inhibition as a means of reducing inflammation-associated trophoblast injury, although such approaches remain preclinical [9]. Similarly, restoration of placental angiogenic signaling through targeted delivery of growth factors or other molecular regulators has been investigated experimentally, with placental gene therapy representing a potential strategy for achieving localized rather than systemic modulation of placental pathways [200].
The metabolic network offers several potential therapeutic entry points, including restoration of nutrient-sensing pathways, modulation of placental transporter activity, and reduction of oxidative or inflammatory stress. Preclinical studies suggest that restoring blunted trophoblast mTOR signaling can restore downstream transporter trafficking and the surface localization of vital amino acid transport proteins such as SNAT2 and LAT1 [21,151]. However, the biological importance of mTOR, amino-acid transport, glucose metabolism, and redox signaling during normal fetal development creates substantial safety constraints [20]. Manipulating these pathways systemically could affect both maternal physiology and fetal development, making placenta-selective strategies particularly important. Current evidence supports continued investigation of mechanism-based interventions rather than routine clinical use of metabolic pathway modulators for FGR. Effective therapies capable of selectively restoring placental nutrient transport remain limited, and experimental strategies require validation in appropriately phenotyped human pregnancies [56,93]. The translational priority is therefore to determine which molecular abnormalities are causal, which are compensatory, and at what gestational stage intervention could restore placental function without disrupting normal developmental signaling.
8.2. Future Therapeutic Perspectives and Safety Constraints
The transition from purely observational clinical surveillance to active mechanism-based modulation represents the next major milestone in the clinical management of fetal growth restriction (FGR). Given that FGR is a complex network disorder rather than an isolated signaling defect, future therapeutic success will fundamentally depend on the precise molecular stratification of patients. Clinical trials must begin to differentiate between early-onset phenotypes, which are predominantly driven by severe anti-angiogenic stress, and late-onset forms that are primarily rooted in placental metabolic and nutrient transport constraints [198,199]. By integrating real-time Doppler velocimetry with multi-omics longitudinal profiling of maternal circulating biomarkers, clinicians can identify which physiological axis requires targeted intervention.
Promising experimental avenues are currently focused on correcting the foundational molecular imbalances that induce trophoblast dysfunction and placental tissue starvation. In the domain of chronic inflammation, targeting the hyperactivated NLRP3/caspase-1 pathway with specific intracellular inhibitors offers a direct method to prevent gasdermin-D-mediated trophoblast pyroptosis, thereby preserving the functional cellular surface required for normal maternal–fetal exchange [9,46]. Concurrently, strategies aimed at rescuing metabolic sensing pathways are gaining traction. Preclinical evidence indicates that the pharmacological or nutritional normalization of blunted trophoblast mTOR signaling can restore downstream p-S6K1 phosphorylation, which in turn upregulates the surface localization and trafficking of vital nutrient transporters such as SNAT2 and LAT1 [106,187]. Furthermore, restoring the placental angiogenic balance through localized growth factor gene delivery or targeted anti-apoptotic therapies (such as stabilizing pro-survival proteins like XIAP or Bcl-2) could alleviate the downstream endothelial injury caused by excessive sFlt-1 production [183,200]. However, translating these laboratory breakthroughs into safe, routine obstetrical practice demands extreme clinical caution and a rigorous critique of systemic delivery methods. Developing disease-modifying agents for pregnant populations carries unprecedented safety and ethical constraints, particularly regarding the high risk of cross-placental fetal exposure. Systemic administration of epigenetic interventions designed to alter aberrant DNA methylation patterns (such as DNA methyltransferase inhibitors) or post-transcriptional networks (such as microRNA mimics or anti-miRs) poses a catastrophic risk of inducing severe teratogenesis, permanent genomic disruption, and the irreversible misalignment of time-sensitive fetal embryonic programming [8,18]. Because these epigenetic marks and non-coding RNAs regulate thousands of developmental pathways simultaneously across both placental and fetal compartments, non-specific systemic bioavailability is functionally prohibitive. Consequently, the development of ligand-functionalized nanoparticles represents an absolute, non-negotiable prerequisite for clinical translation [204,205,206,207]. These surface-engineered, trophoblast-specific nanocarriers are strictly required to encapsulate the molecular payload, navigate the maternal uterine circulation, and selectively target the trophoblast lining without penetrating the fetal blood-placenta barrier. Similarly, the clinical use of regenerative cell-derived therapies, including mesenchymal stem-cell-derived extracellular vesicles, requires exhaustive evaluation regarding maternal systemic vascular hyper-reactivity, localized immunogenicity, and long-term multi-generational safety profiles [208, Until large-scale, international collaborative networks validate these targeted, nanoparticle-delivered strategies through carefully controlled clinical trials, delivery timing guided by precise hemodynamic monitoring will remain the single effective and ethically viable clinical tool against severe placental insufficiency [208,209,210].
8.3. Unified Spatial Transcriptomics and Single-Cell Epigenomics: Mapping the Microenvironmental Topology of FGR
A major limitation of historical placental research in FGR has been its reliance on bulk tissue profiling. By homogenizing whole placental explants, distinct cell-type variations and localized microenvironmental gradients were systematically masked. The true originality of the current molecular landscape lies in the conceptual integration of spatial transcriptomics and single-cell epigenomics (scATAC-seq/scRNA-seq), which shifts the paradigm from global placental failure to a high-resolution, topologically mapped network disorder [8,127].
Emerging spatial profiling demonstrates that placental insufficiency is profoundly regionalized. Under FGR conditions, specific anatomical zones—particularly the proximal anchoring villi and the perimeter of defective maternal spiral arteries—exhibit distinct "hotspots" of chromatin closure and translational arrest [91]. Single-cell multi-omics reveal that extravillous trophoblasts (EVTs) invading these ischemic niches undergo focal epigenetic metaplasia, characterized by localized hypermethylation of the WNT2 promoter and downstream suppression of matrix-remodeling cascades managed by MMP-9 [17]. Conversely, neighboring normoxic compartments often demonstrate hyper-localized compensatory responses, such as the site-specific upregulation of pro-angiogenic splice variants like IGF-IEa and IGF-IEb within the endothelium lining of intact fetal vessels [103,104].
Furthermore, this spatial deconvolution maps the cellular coordinates of the pro-inflammatory shift. The hyperactivation of the NLRP3 inflammasome and subsequent gasdermin-D-mediated pyroptosis are not uniformly distributed across the syncytiotrophoblast layer; rather, they are anatomically anchored to areas of severe local shear stress and persistent maternal vascular malperfusion [9,50]. Mapping these localized cellular interactions provides an entirely original framework for therapeutic design. Instead of systemically administering broad metabolic or angiogenic modulators—which carry prohibitive risks of transplacental fetal toxicity—future interventions can utilize target-selective, ligand-functionalized nanoparticles designed to navigate the placental vascular tree and release their molecular payload exclusively within these epigenetically compromised microenvironmental niches [116,211,212].
9. Conclusions
The synthesis of molecular and clinical evidence presented in this review underscores a fundamental paradigm shift: placental dysfunction in FGR is not the product of an isolated genetic, immune, or vascular defect, but rather the manifestation of a highly integrated, self-reinforcing pathological network. As mapped out across this review, chronic inflammatory activation and NLRP3-mediated trophoblast pyroptosis directly compromise the tissue scaffolding required for matrix metalloproteinase-driven spiral artery remodeling. This initial architectural failure drives the severe angiogenic imbalance defined by the sFlt-1/PlGF axis, which in turn induces downstream endothelial strain and accelerates intrinsic trophoblast apoptosis. Ultimately, this compromised structural and vascular integrity blunts the placenta’s master energetic sensors—most notably the PI3K/AKT/mTOR signaling pathway—culminating in the severe downregulation and trafficking failure of essential amino acid (SNAT2, LAT1) and glucose (GLUT) transporters.
Crucially, this entire structural and metabolic breakdown is directed and sustained by a profound layer of epigenetic and genomic dysregulation. The dynamic placental methylome, alongside distinctive histone modifications and restricted chromatin accessibility managed by subunits like ARID1A, acts as the functional interface through which environmental, maternal, and hypoxic stressors are translated into long-term transcription silencing. When combined with complex post-transcriptional microRNA and long non-coding RNA regulatory circuits, these epigenetic marks lock the placenta into a state of chronic functional insufficiency, cutting off the vital nutritional supply line required for the fetus to achieve its biological growth potential.
Looking forward, this interconnected landscape firmly establishes that traditional, single-target clinical interventions are inherently limited. To transition from passive clinical surveillance to active, mechanism-based care, the future of FGR management lies in biomarker-guided molecular stratification, separating early-onset vascular crises from late-onset metabolic transport failures. Developing targeted, cell-specific therapeutics—such as localized growth factor gene delivery, microRNA modulators, specific inflammasome inhibitors, and stem-cell-derived extracellular vesicles—offers unprecedented promise for restoring placental homeostasis. However, the path to clinical translation demands extreme ethical and pharmacological caution to eliminate any risk of transplacental fetal toxicity or developmental disruption. Until multi-omics profiling is systematically married to functional human organoid models in large-scale collaborative networks, precise clinical staging and the optimization of delivery timing will remain our single effective defense against this devastating pregnancy complication.
Author’s Contributions
F.-N.V. conceived the review, conducted the literature search and review, and wrote the original manuscript. V.-K.V. contributed to the literature search and review and to the preparation of the manuscript. P.T.-N. contributed to the scientific development of the review and critically revised the manuscript. M.V. contributed to the scientific conception and development of the review and critically revised the manuscript for important intellectual content. K.S. contributed to the critical revision of the manuscript. A.P. contributed to the conceptualization and scientific development of the review and supervised the work. All authors have read and agreed to the published version of the manuscript.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
This is a review, so no subjects were involved in the study.
Data Availability Statement
This is a review, and all the data are published and cited in the text.
Funding
This review did not receive any financial support.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Melamed, N.; Baschat, A.; Yinon, Y.; Athanasiadis, A.; Mecacci, F.; Figueras, F.; Berghella, V.; Nazareth, A.; Tahlak, M.; McIntyre, H.D.; Da Silva Costa, F.; Kihara, A.B.; Hadar, E.; McAuliffe, F.; Hanson, M.; Ma, R.C.; Gooden, R.; Sheiner, E.; Kapur, A.; Divakar, H.; Ayres-de-Campos, D.; Hiersch, L.; Poon, L.C.; Kingdom, J.; Romero, R.; Hod, M. FIGO (international Federation of Gynecology and obstetrics) initiative on fetal growth: best practice advice for screening, diagnosis, and management of fetal growth restriction. Int. J. Gynaecol. Obstet. 2021, 152 Suppl 1(Suppl 1), 3–57. [Google Scholar] [CrossRef] [PubMed]
- Chew, L.C.; Osuchukwu, O.O.; Reed, D.J.; Verma, R.P. Fetal growth restriction. In StatPearls [Internet]; StatPearls Publishing: Treasure Island (FL), Jan 2024; Available online: https://www.ncbi.nlm.nih.gov/books/NBK562268/.
- Lees, C.C.; Stampalija, T.; Baschat, A.; da Silva Costa, F.; Ferrazzi, E.; Figueras, F.; Hecher, K.; Kingdom, J.; Poon, L.C.; Salomon, L.J.; Unterscheider, J. ISUOG Practice Guidelines: diagnosis and management of small-for-gestational-age fetus and fetal growth restriction. Ultrasound Obstet. Gynecol. 2020, 56, 298–312. [Google Scholar] [CrossRef] [PubMed]
- Society for Maternal-Fetal Medicine (SMFM). Electronic address: pubs@smfm.org; Martins JG, Biggio JR, Abuhamad A. Society for Maternal-Fetal Medicine Consult Series #52: Diagnosis and management of fetal growth restriction: (Replaces Clinical Guideline Number 3, April 2012). Am J Obstet Gynecol 2020, 223, B2–B17. [Google Scholar] [CrossRef] [PubMed]
- Burton, G.J.; Jauniaux, E. Pathophysiology of placental-derived fetal growth restriction. Am. J. Obstet. Gynecol. 2018, 218, S745–S761. [Google Scholar] [CrossRef] [PubMed]
- Dumolt, J.H.; Powell, T.L.; Jansson, T. Placental Function and the Development of Fetal Overgrowth and Fetal Growth Restriction. Obstet. Gynecol. Clin. North Am. 2021, 48, 247–266. [Google Scholar] [CrossRef] [PubMed]
- Schoots, M.H.; Bourgonje, M.; Bourgonje, A.R.; Prins, J.R.; van Hoorn, E.; Abdulle, A.E.; et al. Oxidative stress biomarkers in fetal growth restriction with and without preeclampsia. Placenta 2021, 115, 87–96. [Google Scholar] [CrossRef] [PubMed]
- Sun, C.; Groom, K.M.; Oyston, C.; Chamley, L.W.; Clark, A.R.; James, J.L. The placenta in fetal growth restriction: What is going wrong? Placenta 2020, 96, 10–18. [Google Scholar] [CrossRef] [PubMed]
- Alfian, I.; Chakraborty, A.; Yong, H.E.J.; Saini, S.; Lau, R.W.K.; Kalionis, B.; Dimitriadis, E.; Alfaidy, N.; Ricardo, S.D.; Samuel, C.S.; Murthi, P. The Placental NLRP3 Inflammasome and Its Downstream Targets, Caspase-1 and Interleukin-6, Are Increased in Human Fetal Growth Restriction: Implications for Aberrant Inflammation-Induced Trophoblast Dysfunction. Cells 2022, 11, 1413. [Google Scholar] [CrossRef] [PubMed]
- Merchant, S.J.; Crocker, I.P.; Baker, P.N.; Tansinda, D.; Davidge, S.T.; Guilbert, L.J. Matrix metalloproteinase release from placental explants of pregnancies complicated by intrauterine growth restriction. J. Soc. Gynecol. Investig. 2004, 11, 97–103. [Google Scholar] [CrossRef] [PubMed]
- Plaks, V.; Rinkenberger, J.; Dai, J.; Flannery, M.; Sund, M.; Kanasaki, K.; Ni, W.; Kalluri, R.; Werb, Z. Matrix metalloproteinase-9 deficiency phenocopies features of preeclampsia and intrauterine growth restriction. Proc. Natl. Acad. Sci. U S A 2013, 110, 11109–14. [Google Scholar] [CrossRef] [PubMed] [PubMed Central]
- Chen, W.; Wei, Q.; Liang, Q.; Song, S.; Li, J. Diagnostic capacity of sFlt-1/PlGF ratio in fetal growth restriction: A systematic review and meta-analysis. Placenta 2022, 127, 37–42. [Google Scholar] [CrossRef] [PubMed]
- Hong, J.; Kumar, S. Circulating biomarkers associated with placental dysfunction and their utility for predicting fetal growth restriction. Clin. Sci. (Lond) 2023, 137, 579–595. [Google Scholar] [CrossRef] [PubMed]
- Stepan, H.; Galindo, A.; Hund, M.; Schlembach, D.; Sillman, J.; Surbek, D.; Vatish, M. Clinical utility of sFlt-1 and PlGF in screening, prediction, diagnosis and monitoring of pre-eclampsia and fetal growth restriction. Ultrasound Obstet. Gynecol. 2023, 61, 168–180. [Google Scholar] [CrossRef] [PubMed]
- Heazell, A.E.; Sharp, A.N.; Baker, P.N.; Crocker, I.P. Intra-uterine growth restriction is associated with increased apoptosis and altered expression of proteins in the p53 pathway in villous trophoblast. Apoptosis 2011, 16, 135–44. [Google Scholar] [CrossRef] [PubMed]
- Hung, T.H.; Wu, C.P.; Chen, S.F. Differential Changes in Akt and AMPK Phosphorylation Regulating mTOR Activity in the Placentas of Pregnancies Complicated by Fetal Growth Restriction and Gestational Diabetes Mellitus With Large-For-Gestational Age Infants. Front Med. 2021, 8, 788969. [Google Scholar] [CrossRef] [PubMed]
- Jin, M.; Xu, S.; Li, J.; Li, L.; Tang, C. Role of ARID1A in the Regulation of Human Trophoblast Migration and Invasion. Reprod. Sci. 2022, 29, 2363–2373. [Google Scholar] [CrossRef] [PubMed]
- Januar, V.; Desoye, G.; Novakovic, B.; Cvitic, S.; Saffery, R. Epigenetic regulation of human placental function and pregnancy outcome: considerations for causal inference. Am. J. Obstet. Gynecol. 2015, 213, S182–S196. [Google Scholar] [CrossRef] [PubMed]
- Vaiman, D. Genes, epigenetics and miRNA regulation in the placenta. Placenta 2017, 52, 127–133. [Google Scholar] [CrossRef] [PubMed]
- Jansson, T.; Powell, T.L. Role of the placenta in fetal programming: underlying mechanisms and potential interventional approaches. Clin. Sci. (Lond) 2007, 113, 1–13. [Google Scholar] [CrossRef] [PubMed]
- Roos, S.; Powell, T.L.; Jansson, T. Placental mTOR links maternal nutrient availability to fetal growth. Biochem Soc. Trans. 2009, 37, 295–8. [Google Scholar] [CrossRef] [PubMed]
- Dimasuay, K.G.; Boeuf, P.; Powell, T.L.; Jansson, T. Placental Responses to Changes in the Maternal Environment Determine Fetal Growth. Front. Physiol. 2016, 7, 12. [Google Scholar] [CrossRef] [PubMed]
- Kany, S.; Vollrath, J.T.; Relja, B. Cytokines in Inflammatory Disease. Int. J. Mol. Sci. 2019, 20, 6008. [Google Scholar] [CrossRef] [PubMed]
- Dong, C. Cytokine Regulation and Function in T Cells. Annu Rev. Immunol. 2021, 39, 51–76. [Google Scholar] [CrossRef] [PubMed]
- Wautier, J.L.; Wautier, M.P. Pro- and Anti-Inflammatory Prostaglandins and Cytokines in Humans: A Mini Review. Int. J. Mol. Sci. 2023, 24, 9647. [Google Scholar] [CrossRef] [PubMed]
- Opal, S.M.; DePalo, V.A. Anti-inflammatory cytokines. Chest 2000, 117, 1162–72. [Google Scholar] [CrossRef] [PubMed]
- Cheng, S.B.; Sharma, S. Interleukin-10: a pleiotropic regulator in pregnancy. Am. J. Reprod. Immunol. 2015, 73, 487–500. [Google Scholar] [CrossRef] [PubMed]
- García-Morales, A.; Lomas-Soria, C.; Granados-Higa, G.; García-Quiroz, J.; Avila, E.; Olmos-Ortiz, A.; et al. Inflammation in Pregnancy: Key Drivers, Signaling Pathways and Associated Complications. Arch. Med. Res. 2026, 57, 103301. [Google Scholar] [CrossRef] [PubMed]
- Miranda, J.; Maestre, N.; Devia, M.; Zapata, R.; Ochoa-Díaz, M.M.; Annicchiarico, W. Inflammation at the Maternal-Fetal Interface: Mechanisms Linking Maternal-Fetal Immunity to Preeclampsia and Fetal Growth Restriction. Int. J. Mol. Sci. 2026, 27, 3954. [Google Scholar] [CrossRef] [PubMed]
- Raghupathy, R.; Al-Azemi, M.; Azizieh, F. Intrauterine growth restriction: cytokine profiles of trophoblast antigen-stimulated maternal lymphocytes. Clin. Dev. Immunol. 2012, 2012, 734865. [Google Scholar] [CrossRef] [PubMed]
- Kırıcı, P.; Çağıran, F.T.; Kalı, Z.; Tanrıverdi, E.S.; Mavral, N.; Ecin, S.M. Determination of maternal serum pro-inflammatory cytokine changes in intrauterine growth restriction. Eur. Rev. Med. Pharmacol. Sci. 2023, 27, 1996–2001. [Google Scholar] [CrossRef] [PubMed]
- Mancuso, P. The role of adipokines in chronic inflammation. Immunotargets Ther. 2016, 5, 47–56. [Google Scholar] [CrossRef] [PubMed]
- Varra, F.N.; Varras, M.; Varra, V.K.; Theodosis-Nobelos, P. Molecular and pathophysiological relationship between obesity and chronic inflammation in the manifestation of metabolic dysfunctions and their inflammation-mediating treatment options (Review). Mol. Med. Rep. 2024, 29, 95. [Google Scholar] [CrossRef] [PubMed]
- Lau, C.W. Central Role of adipose tissue in pregnancy and lactation. Maternal-Fetal and Neonatal Endocrinology. In Physiology, Pathophysiology and Clinical Management; Kovacs, C.S., Deal, C.L., Eds.; 2020; pp. 147–158. [Google Scholar]
- Downs, T.; da Silva Costa, F.; de Freitas Paganoti, C.; Holland, O.J.; Hryciw, D.H. Adiponectin and Leptin during Pregnancy: A Systematic Review of Their Association with Pregnancy Disorders, Fetal Growth and Placental Function. Endocrines 2024, 5, 382–394. [Google Scholar] [CrossRef]
- Van Mieghem, T.; Doherty, A.; Baczyk, D.; Drewlo, S.; Baud, D.; Carvalho, J.; Kingdom, J. Apelin in Normal Pregnancy and Pregnancies Complicated by Placental Insufficiency. Reprod. Sci. 2016, 23, 1037–43. [Google Scholar] [CrossRef] [PubMed]
- Loukas, N.; Vrachnis, D.; Antonakopoulos, N.; Stavros, S.; Machairiotis, N.; Fotiou, A.; Christodoulaki, C.; Lolos, M.; Maroudias, G.; Potiris, A.; et al. Decoding Apelin: Its Role in Metabolic Programming, Fetal Growth, and Gestational Complications. Children 2024, 11, 1270. [Google Scholar] [CrossRef] [PubMed]
- Clemente-Suárez, V.J.; Redondo-Flórez, L.; Beltrán-Velasco, A.I.; Martín-Rodríguez, A.; Martínez-Guardado, I.; Navarro-Jiménez, E.; Laborde-Cárdenas, C.C.; Tornero-Aguilera, J.F. The Role of Adipokines in Health and Disease. Biomedicines 2023, 11, 1290. [Google Scholar] [CrossRef] [PubMed]
- Kabbani, N.; Blüher, M.; Stepan, H.; Stumvoll, M.; Ebert, T.; Tönjes, A.; Schrey-Petersen, S. Adipokines in Pregnancy: A Systematic Review of Clinical Data. Biomedicines 2023, 11, 1419. [Google Scholar] [CrossRef] [PubMed]
- Sapantzoglou, I.; Vlachos, D.E.; Papageorgiou, D.; Varthaliti, A.; Rodolaki, K.; Daskalaki, M.A.; Psarris, A.; Pergialiotis, V.; Stavros, S.; Daskalakis, G.; Papapanagiotou, A. Maternal Blood Adipokines and Their Association with Fetal Growth: A Meta-Analysis of the Current Literature. J. Clin. Med. 2024, 13, 1667. [Google Scholar] [CrossRef] [PubMed]
- Kelley, N.; Jeltema, D.; Duan, Y.; He, Y. The NLRP3 Inflammasome: An Overview of Mechanisms of Activation and Regulation. Int. J. Mol. Sci. 2019, 20, 3328. [Google Scholar] [CrossRef] [PubMed]
- Xu, J.; Núñez, G. The NLRP3 inflammasome: activation and regulation. Trends Biochem. Sci. 2023, 48, 331–344. [Google Scholar] [CrossRef] [PubMed]
- Gomez-Lopez, N.; Motomura, K.; Miller, D.; Garcia-Flores, V.; Galaz, J.; Romero, R. Inflammasomes: Their Role in Normal and Complicated Pregnancies. J. Immunol. 2019, 203, 2757–2769. [Google Scholar] [CrossRef] [PubMed]
- Balci, C.N.; Acar, N. NLRP3 inflammasome pathway, the hidden balance in pregnancy: A comprehensive review. J. Reprod. Immunol. 2024, 161, 104173. [Google Scholar] [CrossRef] [PubMed]
- Cheng, S.B.; Nakashima, A.; Huber, W.J.; Davis, S.; Banerjee, S.; Huang, Z.; Saito, S.; Sadovsky, Y.; Sharma, S. Pyroptosis is a critical inflammatory pathway in the placenta from early onset preeclampsia and in human trophoblasts exposed to hypoxia and endoplasmic reticulum stressors. Cell Death Dis. 2019, 10, 927. [Google Scholar] [CrossRef] [PubMed]
- Li, W.; Zheng, R.; Shi, C.; Chen, D.; Sun, Y.; Hu, B.; Xu, G. Role of pyroptosis in pregnancy-related diseases. PeerJ 2025, 13, e19922. [Google Scholar] [CrossRef] [PubMed]
- Chen, J.; Khalil, R.A. Matrix Metalloproteinases in Normal Pregnancy and Preeclampsia. Prog. Mol. Biol. Transl. Sci. 2017, 148, 87–165. [Google Scholar] [CrossRef] [PubMed]
- Nikolov, A.; Popovski, N. Role of Gelatinases MMP-2 and MMP-9 in Healthy and Complicated Pregnancy and Their Future Potential as Preeclampsia Biomarkers. Diagnostics 2021, 11, 480. [Google Scholar] [CrossRef] [PubMed]
- Cheng, J.C.; Meng, Q.; Zhang, Q.; Zhang, L.; Chen, J.; Song, T.; Fang, L.; Sun, Y.P. WNK1 mediates amphiregulin-induced MMP9 expression and cell invasion in human extravillous trophoblast cells. Mol. Cell Endocrinol. 2023, 576, 112038. [Google Scholar] [CrossRef] [PubMed]
- Brouwers, L.; de Gier, S.; Vogelvang, T.E.; Veerbeek, J.H.W.; Franx, A.; van Rijn, B.B.; Nikkels, P.G.J. Prevalence of placental bed spiral artery pathology in preeclampsia and fetal growth restriction: A prospective cohort study. Placenta 2024, 156, 1–9. [Google Scholar] [CrossRef] [PubMed]
- Gumina, D.L.; Su, E.J. Mechanistic insights into the development of severe fetal growth restriction. Clin. Sci. (Lond) 2023, 137, 679–695. [Google Scholar] [CrossRef] [PubMed]
- Kolawole, E.; Duggirala, A.; Gronow, O.; Lovett, A.; Hu, J.; Tan, B.K. Differential Expression of Maternal Plasma microRNAs and Their Respective Gene Targets Can Predict Early Fetal Growth Restriction. Life 2025, 15, 167. [Google Scholar] [CrossRef] [PubMed] [PubMed Central]
- Bardill, J.R.; Eason, C.R.; Wood, H.; Breckenfelder, C.; Gallagher, L.T.; Crew, M.; Karimpour-Fard, A.; Sucharov, C.C.; Powell, T.L.; Wright, C.J.; Derderian, S.C. Investigating trophoblast invasion and angiogenesis expression changes in a caloric deficient mouse model of fetal growth restriction. Reprod. Biol. 2026, 26, 101179. [Google Scholar] [CrossRef] [PubMed]
- Wang, Y.; Zhao, S. Chapter 7 Angiogenic Factors. In Vascular Biology of the Placenta; Morgan & Claypool Life Sciences: San Rafael (CA), 2010; Available online: https://www.ncbi.nlm.nih.gov/books/NBK53255/.
- Gourvas, V.; Dalpa, E.; Konstantinidou, A.; Vrachnis, N.; Spandidos, D.A.; Sifakis, S. Angiogenic factors in placentas from pregnancies complicated by fetal growth restriction (review). Mol. Med. Rep. 2012, 6, 23–7. [Google Scholar] [CrossRef] [PubMed]
- Umapathy, A.; Clark, A.; Sehgal, A.; Karanam, V.; Rajaraman, G.; Kalionis, B.; Jones, H.N.; James, J.; Murthi, P. Molecular regulators of defective placental and cardiovascular development in fetal growth restriction. Clin. Sci. (Lond) 2024, 138, 761–775. [Google Scholar] [CrossRef] [PubMed]
- Villalaín, C.; Galindo, A.; D'Antonio, F.; Herraiz, I. Clinical use of angiogenesis biomarkers in fetal growth restriction: a narrative review. J. Matern Fetal Neonatal Med. 2025, 38, 2589630. [Google Scholar] [CrossRef] [PubMed]
- Zhu, J.Y.; Pang, Z.J.; Yu, Y.H. Regulation of trophoblast invasion: the role of matrix metalloproteinases. Rev. Obstet. Gynecol. 2012, 5, e137-43. [Google Scholar] [PubMed]
- Zhu, J.; Zhong, M.; Pang, Z.; Yu, Y. Dysregulated expression of matrix metalloproteinases and their inhibitors may participate in the pathogenesis of pre-eclampsia and fetal growth restriction. Early Hum. Dev. 2014, 90, 657–64. [Google Scholar] [CrossRef] [PubMed]
- Autiero, M.; Luttun, A.; Tjwa, M.; Carmeliet, P. Placental growth factor and its receptor, vascular endothelial growth factor receptor-1: novel targets for stimulation of ischemic tissue revascularization and inhibition of angiogenic and inflammatory disorders. J. Thromb. Haemost. 2003, 1, 1356–70. [Google Scholar] [CrossRef] [PubMed]
- Yao, Y.G.; Yang, H.S.; Cao, Z.; Danielsson, J.; Duh, E.J. Upregulation of placental growth factor by vascular endothelial growth factor via a post-transcriptional mechanism. FEBS Lett. 2005, 579, 1227–34. [Google Scholar] [CrossRef] [PubMed]
- Chappell, L.C.; Duckworth, S.; Seed, P.T.; Griffin, M.; Myers, J.; Mackillop, L.; Simpson, N.; Waugh, J.; Anumba, D.; Kenny, L.C.; Redman, C.W.; Shennan, A.H. Diagnostic accuracy of placental growth factor in women with suspected preeclampsia: a prospective multicenter study. Circulation 2013, 128, 2121–31. [Google Scholar] [CrossRef] [PubMed]
- Albonici, L.; Benvenuto, M.; Focaccetti, C.; Cifaldi, L.; Miele, M.T.; Limana, F.; Manzari, V.; Bei, R. PlGF Immunological Impact during Pregnancy. Int. J. Mol. Sci. 2020, 21, 8714. [Google Scholar] [CrossRef] [PubMed]
- Vrachnis, N.; Kalampokas, E.; Sifakis, S.; Vitoratos, N.; Kalampokas, T.; Botsis, D.; Iliodromiti, Z. Placental growth factor (PlGF): a key to optimizing fetal growth. J. Matern. Fetal Neonatal. Med. 2013, 26, 995–1002. [Google Scholar] [CrossRef] [PubMed]
- Hernández-Baraza, L.; Brito-Casillas, Y.; Valverde-Tercedor, C.; Recio, C.; Fernández-Pérez, L.; Guerra, B.; Wägner, A.M. Mechanisms of Fetal Overgrowth in Gestational Diabetes: The Potential Role of SOCS2. Nutrients 2025, 17, 1519. [Google Scholar] [CrossRef] [PubMed]
- Huang, H.; Wang, S. Prediction of Fetal Growth Restriction Using Serum PlGF Combined with PAPP-A in Early Pregnancy. Int. J. Womens Health 2025, 17, 2845–2851. [Google Scholar] [CrossRef] [PubMed]
- Hong, J.; Kumar, S. Circulating biomarkers associated with placental dysfunction and their utility for predicting fetal growth restriction. Clin. Sci. (Lond) 2023, 137, 579–595. [Google Scholar] [CrossRef] [PubMed]
- Shibuya, M. Vascular Endothelial Growth Factor (VEGF) and Its Receptor (VEGFR) Signaling in Angiogenesis: A Crucial Target for Anti- and Pro-Angiogenic Therapies. Genes Cancer 2011, 2, 1097–105. [Google Scholar] [CrossRef] [PubMed]
- Chen, D.; Zheng, J. Regulation of Placental Angiogenesis. Microcirculation 2014, 21, 15–25. [Google Scholar] [CrossRef] [PubMed]
- Girardi, G.; Yarilin, D.; Thurman, J.M.; Holers, V.M.; Salmon, J.E. Complement activation induces dysregulation of angiogenic factors and causes fetal rejection and growth restriction. J. Exp. Med. 2006, 203, 2165–75. [Google Scholar] [CrossRef] [PubMed]
- Azliana, A.F.; Zainul-Rashid, M.R.; Chandramaya, S.F.; Farouk, W.I.; Nurwardah, A.; Wong, Y.P.; Tan, G.C. Vascular endothelial growth factor expression in placenta of hypertensive disorder in pregnancy. Indian J. Pathol. Microbiol. 2017, 60, 515–520. [Google Scholar] [CrossRef] [PubMed]
- Alahakoon, T.I.; Zhang, W.; Arbuckle, S.; Zhang, K.; Lee, V. Reduced angiogenic factor expression in intrauterine fetal growth restriction using semiquantitative immunohistochemistry and digital image analysis. J. Obstet. Gynaecol. Res. 2018, 44, 861–872. [Google Scholar] [CrossRef] [PubMed]
- Song, W.; Guo, Q.; Puttabyatappa, M.; Elangovan, V.R.; Wang, J.; Li, F.; Liu, F.; Bi, X.; Li, H.; Fu, G.; Padmanabhan, V.; Wu, X. FGR-associated placental insufficiency and capillary angiogenesis involves disruptions in human placental miRNAs and mRNAs. Heliyon 2024, 10, e28007. [Google Scholar] [CrossRef] [PubMed]
- Ahmed, A.; Dunk, C.; Ahmad, S.; Khaliq, A. Regulation of placental vascular endothelial growth factor (VEGF) and placenta growth factor (PIGF) and soluble Flt-1 by oxygen--a review. Placenta 2000, 21 Suppl A, S16–24. [Google Scholar] [CrossRef] [PubMed]
- Soares, M.J.; Iqbal, K.; Kozai, K. Hypoxia and Placental Development. Birth Defects Res. 2017, 109, 1309–1329. [Google Scholar] [CrossRef] [PubMed]
- Papapanagiotou, A.; Daskalaki, M.A.; Gargalionis, A.N.; Margoni, A.; Domali, A.; Daskalakis, G.; Papavassiliou, A.G. The Role of Angiogenetic Factors in Preeclampsia. Int. J. Mol. Sci. 2025, 26, 10431. [Google Scholar] [CrossRef] [PubMed]
- Iftikhar, M.; Sharif, S.; Khan, S.; Ali, I.; Lodhi, M.S.; Shah, S.I.A.; Khan, M.I.U. Angiogenic imbalance, inflammation, and oxidative stress in patients with fetal growth restriction: A case-control study. Afr. J. Reprod. Health 2025, 29, 39–53. [Google Scholar] [CrossRef] [PubMed]
- Gaba, S.; Sahu, M.; Chauhan, N.; Jain, U. Transforming growth factor alpha: Key insights into physiological role, cancer therapeutics, and biomarker potential (A review). Int. J. Biol. Macromol. 2025, 310, 143212. [Google Scholar] [CrossRef] [PubMed]
- Waye, A.A.; Moeller, J.; Veiga-Lopez, A. Epidermal growth factor receptor in placental health and disease: pathways, dysfunction, and chemical disruption. Toxicol. Sci. 2025, 205, 11–27. [Google Scholar] [CrossRef] [PubMed]
- Clemente, L.; Bird, I.M. The epidermal growth factor receptor in healthy pregnancy and preeclampsia. J. Mol. Endocrinol. 2022, 70, e220105. [Google Scholar] [CrossRef] [PubMed]
- Briana, D.D.; Liosi, S.; Gourgiotis, D.; Boutsikou, M.; Marmarinos, A.; Baka, S.; Hassiakos, D.; Malamitsi-Puchner, A. Fetal concentrations of the growth factors TGF-α and TGF-β1 in relation to normal and restricted fetal growth at term. Cytokine 2012, 60, 157–61. [Google Scholar] [CrossRef] [PubMed]
- Wen, B.; Liao, H.; Lin, W.; Li, Z.; Ma, X.; Xu, Q.; Yu, F. The Role of TGF-β during Pregnancy and Pregnancy Complications. Int. J. Mol. Sci. 2023, 24, 16882. [Google Scholar] [CrossRef] [PubMed]
- Schilling, B.; Yeh, J. Transforming growth factor-beta(1), -beta(2), -beta(3) and their type I and II receptors in human term placenta. Gynecol Obstet Invest. 2000, 50, 19–23, Simpson et al., 2002. [Google Scholar] [CrossRef] [PubMed]
- Prossler, J.; Chen, Q.; Chamley, L.; James, J.L. The relationship between TGFβ, low oxygen and the outgrowth of extravillous trophoblasts from anchoring villi during the first trimester of pregnancy. Cytokine 2014, 68, 9–15. [Google Scholar] [CrossRef] [PubMed]
- Brkić, J.; Dunk, C.; O'Brien, J.; Fu, G.; Nadeem, L.; Wang, Y.L.; Rosman, D.; Salem, M.; Shynlova, O.; Yougbaré, I.; Ni, H.; Lye, S.J.; Peng, C. MicroRNA-218-5p Promotes Endovascular Trophoblast Differentiation and Spiral Artery Remodeling. Mol. Ther. 2018, 26, 2189–2205. [Google Scholar] [CrossRef] [PubMed]
- Chuva de Sousa Lopes, S.M.; Alexdottir, M.S.; Valdimarsdottir, G. The TGFβ Family in Human Placental Development at the Fetal-Maternal Interface. Biomolecules 2020, 10, 453. [Google Scholar] [CrossRef] [PubMed]
- Yang, D.; Dai, F.; Yuan, M.; Zheng, Y.; Liu, S.; Deng, Z.; Tan, W.; Chen, L.; Zhang, Q.; Zhao, X.; Cheng, Y. Role of Transforming Growth Factor-β1 in Regulating Fetal-Maternal Immune Tolerance in Normal and Pathological Pregnancy. Front Immunol. 2021, 12, 689181. [Google Scholar] [CrossRef] [PubMed]
- Horvat Mercnik, M.; Schliefsteiner, C.; Sanchez-Duffhues, G.; Wadsack, C. TGFβ signalling: a nexus between inflammation, placental health and preeclampsia throughout pregnancy. Hum. Reprod. Update 2024, 30, 442–471. [Google Scholar] [CrossRef] [PubMed]
- Adu-Gyamfi, E.A.; Ding, Y.B.; Wang, Y.X. Regulation of placentation by the transforming growth factor beta superfamily†. Biol. Reprod. 2020, 102, 18–26. [Google Scholar] [CrossRef] [PubMed]
- Burton, G.J.; Jauniaux, E. The cytotrophoblastic shell and complications of pregnancy. Placenta 2017, 60, 134–139. [Google Scholar] [CrossRef] [PubMed]
- Burton, G.J.; Cindrova-Davies, T.; Yung, H.W.; Jauniaux, E. HYPOXIA AND REPRODUCTIVE HEALTH: Oxygen and development of the human placenta. Reproduction 2021, 161, F53–F65. [Google Scholar] [CrossRef] [PubMed]
- Agrogiannis, G.D.; Sifakis, S.; Patsouris, E.S.; Konstantinidou, A.E. Insulin-like growth factors in embryonic and fetal growth and skeletal development (Review). Mol. Med. Rep. 2014, 10, 579–84. [Google Scholar] [CrossRef] [PubMed]
- Sferruzzi-Perri, A.N.; Sandovici, I.; Constancia, M.; Fowden, A.L. Placental phenotype and the insulin-like growth factors: resource allocation to fetal growth. J. Physiol. 2017, 595, 5057–5093. [Google Scholar] [CrossRef] [PubMed]
- Soliman, A.T.; Alyafei, F.; Alaaraj, N.; Ahmed, S.; Hamed, N.; Elsiddig, S. Placental hormones, IGF-1, and early-life growth: endocrine links between birth size and infant metabolic programming-a systematic review. Eur. J. Pediatr. 2026, 185, 313. [Google Scholar] [CrossRef] [PubMed]
- Baxter, R.C. Signaling Pathways of the Insulin-like Growth Factor Binding Proteins. Endocr. Rev. 2023, 44, 753–778. [Google Scholar] [CrossRef] [PubMed]
- Ahmadi, S.M.; Perez, M.L.; Guardia, C.M. Secretion of placental peptide hormones: functions and trafficking. Front Endocrinol. 2025, 16, 1584303. [Google Scholar] [CrossRef] [PubMed]
- Szydlowska-Gladysz, J.; Gorecka, A.E.; Stepien, J.; Rysz, I.; Ben-Skowronek, I. IGF-1 and IGF-2 as Molecules Linked to Causes and Consequences of Obesity from Fetal Life to Adulthood: A Systematic Review. Int. J. Mol. Sci. 2024, 25, 3966. [Google Scholar] [CrossRef] [PubMed]
- Randhawa, R.S. The insulin-like growth factor system and fetal growth restrictionn. Pediatr. Endocrinol. Rev. 2008, 6, 235–40. [Google Scholar] [CrossRef]
- Koutsaki, M.; Sifakis, S.; Zaravinos, A.; Koutroulakis, D.; Koukoura, O.; Spandidos, D.A. Decreased placental expression of hPGH, IGF-I and IGFBP-1 in pregnancies complicated by fetal growth restriction. Growth Horm. IGF Res. 2011, 21, 31–6. [Google Scholar] [CrossRef] [PubMed]
- Street, M.E.; Seghini, P.; Fieni, S.; Ziveri, M.A.; Volta, C.; Martorana, D.; Viani, I.; Gramellini, D.; Bernasconi, S. Changes in interleukin-6 and IGF system and their relationships in placenta and cord blood in newborns with fetal growth restriction compared with controls. Eur. J. Endocrinol. 2006, 155, 567–74. [Google Scholar] [CrossRef] [PubMed]
- Wilson, R.L.; Troja, W.; Sumser, E.K.; Maupin, A.; Lampe, K.; Jones, H.N. Insulin-like growth factor 1 signaling in the placenta requires endothelial nitric oxide synthase to support trophoblast function and normal fetal growth. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2021, 320, R653–R662. [Google Scholar] [CrossRef] [PubMed]
- Sandovici, I.; Georgopoulou, A.; Pérez-García, V.; Hufnagel, A.; López-Tello, J.; Lam, B.Y.H.; Schiefer, S.N.; Gaudreau, C.; Santos, F.; Hoelle, K.; Yeo, G.S.H.; Burling, K.; Reiterer, M.; Fowden, A.L.; Burton, G.J.; Branco, C.M.; Sferruzzi-Perri, A.N.; Constância, M. The imprinted Igf2-Igf2r axis is critical for matching placental microvasculature expansion to fetal growth. Dev. Cell 2022, 57, 63–79.e8. [Google Scholar] [CrossRef] [PubMed]
- Fasoulopoulos, A.; Varras, M.; Varra, F.N.; Philippou, A.; Myoteri, D.; Varra, V.K.; Kouroglou, E.; Gryparis, A.; Papadopetraki, A.; Vlachos, I.; Papadopoulos, K.; Koutsilieris, M.; Konstantinidou, A.E. Expression of the IGF-1Ea isoform in human placentas from third trimester normal and idiopathic intrauterine growth restriction singleton pregnancies: Correlations with clinical and histopathological parameters. Mol. Med. Rep. 2025, 31, 69. [Google Scholar] [CrossRef] [PubMed]
- Fasoulopoulos, A.; Varras, M.; Varra, F.-N.; Varra, V.-K.; Philippou, A.; Gryparis, A.; Papadopetraki, A.; Stellatos, P.; Pesiridou, A.; Paparizou, K.; et al. IGF-1Eb Isoform Immunoreactivity May Be Associated with Placental Dysfunction and Vascular Pathology in Fetal Growth Restriction (FGR). Biomolecules 2026, 16, 1281. [Google Scholar] [CrossRef] [PubMed]
- Abu Shehab, M.; Khosravi, J.; Han, V.K.; Shilton, B.H.; Gupta, M.B. Site-specific IGFBP-1 hyper-phosphorylation in fetal growth restriction: clinical and functional relevance. J. Proteome Res. 2010, 9, 1873–81. [Google Scholar] [CrossRef] [PubMed]
- Rosario, F.J.; Chopra, A.; Biggar, K.; Powell, T.L.; Gupta, M.B.; Jansson, T. Placental Remote Control of Fetal Metabolism: Trophoblast mTOR Signaling Regulates Liver IGFBP-1 Phosphorylation and IGF-1 Bioavailability. Int. J. Mol. Sci. 2023, 24, 7273. [Google Scholar] [CrossRef] [PubMed]
- Damerill, I.; Biggar, K.K.; Abu Shehab, M.; Li, S.S.; Jansson, T.; Gupta, M.B. Hypoxia Increases IGFBP-1 Phosphorylation Mediated by mTOR Inhibition. Mol. Endocrinol. 2016, 30, 201–16. [Google Scholar] [CrossRef] [PubMed]
- Crosley, E.J.; Dunk, C.E.; Beristain, A.G.; Christians, J.K. IGFBP-4 and -5 are expressed in first-trimester villi and differentially regulate the migration of HTR-8/SVneo cells. Reprod. Biol. Endocrinol. 2014, 12, 123. [Google Scholar] [CrossRef] [PubMed]
- Yao, Z.; Lin, M.; Lin, T.; Gong, X.; Qin, P.; Li, H.; Kang, T.; Ye, J.; Zhu, Y.; Hong, Q.; Liu, Y.; Li, Y.; Wang, J.; Fang, F. The expression of IGFBP-5 in the reproductive axis and effect on the onset of puberty in female rats. Reprod. Biol. Endocrinol. 2022, 20, 100. [Google Scholar] [CrossRef] [PubMed]
- Witkowska-Sędek, E.; Pyrżak, B. Chronic inflammation and the growth hormone/insulin-like growth factor-1 axis. Cent. Eur. J. Immunol. 2020, 45, 469–75. [Google Scholar] [CrossRef] [PubMed]
- Burton, G.J.; Jauniaux, E. Pathophysiology of placental-derived fetal growth restriction. Am. J. Obstet. Gynecol. 2018, 218, S745–S761. [Google Scholar] [CrossRef] [PubMed]
- Zhou, H.; Zhao, C.; Wang, P.; Yang, W.; Zhu, H.; Zhang, S. Regulators involved in trophoblast syncytialization in the placenta of intrauterine growth restriction. Front Endocrinol. 2023, 14, 1107182. [Google Scholar] [CrossRef] [PubMed]
- Vornic, I.; Caprariu, R.; Novacescu, D.; Barb, A.C.; Buciu, V.; Băloi, A.; Szekely, D.; Suciu, C.S.; Dumitru, C.; Patrascu, R.; et al. Molecular Insights into Human Placentation: From Villous Morphogenesis to Pathological Pathways and Translational Biomarkers. Int. J. Mol. Sci. 2025, 26, 9483. [Google Scholar] [CrossRef] [PubMed]
- Moraru, L.; Moraru, R.; Mitranovici, M.I.; Micu, R. Altered PAPP-A and Placental Thickness in Pre-Eclampsia and Intrauterine Growth Restriction: A Pilot Study. J. Clin. Med. 2026, 15, 1607. [Google Scholar] [CrossRef] [PubMed]
- Arnouts, L.; Terwingen, J.; Van Damme, K.; Mannaerts, D. The added value of the sFlt-1/PlGF ratio in pregnant women with intrauterine growth restriction (IUGR) with or without preeclampsia on adverse pregnancy outcomes and neonatal morbidities: a retrospective study. BMC Pregnancy Childbirth 2025, 25, 959. [Google Scholar] [CrossRef] [PubMed]
- Jena, M.K.; Sharma, N.R.; Petitt, M.; Maulik, D.; Nayak, N.R. Pathogenesis of Preeclampsia and Therapeutic Approaches Targeting the Placenta. Biomolecules 2020, 10, 953. [Google Scholar] [CrossRef] [PubMed]
- Gaccioli, F.; Sovio, U.; Gong, S.; Cook, E.; Charnock-Jones, D.S.; Smith, G.C.S. Increased Placental sFLT1 (Soluble fms-Like Tyrosine Kinase Receptor-1) Drives the Antiangiogenic Profile of Maternal Serum Preceding Preeclampsia but Not Fetal Growth Restriction. Hypertension 2023, 80, 325–334. [Google Scholar] [CrossRef] [PubMed]
- Byrne, Z.; Brennan, S.; Watson, D.; Rudd, D.; Kandasamy, Y. Maternal sFlt-1/PlGF Ratio to Distinguish Pathological Fetal Growth Restriction From Constitutional Smallness: Systematic Review. BJOG 2026, 133, 922–931. [Google Scholar] [CrossRef] [PubMed]
- Stepan, H.; Hund, M.; Andraczek, T. Clinical utility of sFlt-1 and PlGF in screening, prediction, diagnosis and monitoring of pre-eclampsia and fetal growth restriction. Ultrasound Obstet. Gynecol. 2023, 61, 168–180. [Google Scholar] [CrossRef] [PubMed]
- Indeglia, A.; Murphy, M.E. Elucidating the chain of command: our current understanding of critical target genes for p53-mediated tumor suppression. Crit. Rev. Biochem Mol. Biol. 2024, 59, 128–138. [Google Scholar] [CrossRef] [PubMed]
- Heazell, A.E.; Sharp, A.N.; Baker, P.N.; Crocker, I.P. Intra-uterine growth restriction is associated with increased apoptosis and altered expression of proteins in the p53 pathway in villous trophoblast. Apoptosis 2011, 16, 135–44. [Google Scholar] [CrossRef] [PubMed]
- Levy, R.; Smith, S.D.; Yusuf, K.; Huettner, P.C.; Kraus, F.T.; Sadovsky, Y.; Nelson, D.M. Trophoblast apoptosis from pregnancies complicated by fetal growth restriction is associated with enhanced p53 expression. Am. J. Obstet. Gynecol. 2002, 186, 1056–61. [Google Scholar] [CrossRef] [PubMed]
- Meng, M.H.; Wu, X.; Qin, T.; Mo, W.Y.; Long, X.G.; Li, Y.; Zhang, P.; Lu, J.N.; Pan, D.; Zhang, X.Q. Shp2 regulates the trophoblast cell cycle progression through p53-p21 pathway modulation. Biochem Biophys. Res. Commun. 2025, 776, 152209. [Google Scholar] [CrossRef] [PubMed]
- Guo, G.; Zhou, T.; Ren, F.; Sun, J.; Deng, D.; Huang, X.; Wassie, T.; Qazi, I.H.; Wu, X. Effect of Maternal Catalase Supplementation on Reproductive Performance, Antioxidant Activity and Mineral Transport in Sows and Piglets. Animals 2022, 12, 828. [Google Scholar] [CrossRef] [PubMed]
- Huang, Y.; Xu, L.; Fu, H.; Zhang, W.; Zeng, M.; Lee, S.; Li, S.; Lan, G.; Huang, Y.; Ruan, D.; Zhang, Q.; Wang, C.; Zhang, W.; Chen, A.C.H.; Fong, S.W.; Lee, Y.L.; Yeung, W.S.B.; Wong, J.W.H.; Dougan, G.; Li, L.; Liu, J.; Javed, A.; Liu, P. Tumor suppressor protein p53 governs human trophoblast lineage development. Cell Rep. 2025, 44, 116310. [Google Scholar] [CrossRef] [PubMed]
- Dong, Y.; Zhang, L.; Zhang, S.; Bai, Y.; Chen, H.; Sun, X.; Yong, W.; Li, W.; Colvin, S.C.; Rhodes, S.J.; Shou, W.; Zhang, Z.Y. Phosphatase of regenerating liver 2 (PRL2) is essential for placental development by down-regulating PTEN (Phosphatase and Tensin Homologue Deleted on Chromosome 10) and activating Akt protein. J. Biol. Chem. 2012, 287, 32172–9. [Google Scholar] [CrossRef] [PubMed]
- Huang, B.; Wang, H.; An, Z.; Yang, Z.; Cao, J.; Wang, L.; Luo, X.; Qi, H. Compromised Peroxisome Proliferator-Activated Receptor γ-Mediated Impaired Placental Glucose Transport Via the Phosphatidylinositol 3-Kinase/Protein Kinase B Signaling Pathway Is Associated With Fetal Growth Restriction. Lab Invest. 2025, 105, 104103. [Google Scholar] [CrossRef] [PubMed]
- Laguë, M.N.; Detmar, J.; Paquet, M.; Boyer, A.; Richards, J.S.; Adamson, S.L.; Boerboom, D. Decidual PTEN expression is required for trophoblast invasion in the mouse. Am. J. Physiol. Endocrinol. Metab. 2010, 299, E936-46. [Google Scholar] [CrossRef] [PubMed] [PubMed Central]
- Xue, P.; Fan, W.; Diao, Z.; Li, Y.; Kong, C.; Dai, X.; Peng, Y.; Chen, L.; Wang, H.; Hu, Y.; Hu, Z. Up-regulation of PTEN via LPS/AP-1/NF-κB pathway inhibits trophoblast invasion contributing to preeclampsia. Mol. Immunol. 2020, 118, 182–190. [Google Scholar] [CrossRef] [PubMed]
- Fantone, S.; Mazzucchelli, R.; Giannubilo, S.R.; Ciavattini, A.; Marzioni, D.; Tossetta, G. AT-rich interactive domain 1A protein expression in normal and pathological pregnancies complicated by preeclampsia. Histochem Cell Biol. 2020, 154, 339–346. [Google Scholar] [CrossRef] [PubMed]
- Jin, M.; Xu, S.; Li, J.; Li, L.; Tang, C. Role of ARID1A in the Regulation of Human Trophoblast Migration and Invasion. Reprod. Sci. 2022, 29, 2363–2373. [Google Scholar] [CrossRef] [PubMed]
- Sun, C.; Groom, K.M.; Oyston, C.; Chamley, L.W.; Clark, A.R.; James, J.L. The placenta in fetal growth restriction: What is going wrong? Placenta 2020, 96, 10–18. [Google Scholar] [CrossRef] [PubMed]
- Huang, Y.; Yang, X.; Wang, Y.; Nai, Y.; Ji, L.; Zhu, H.; Lai, R.; Wang, Q.T.; Hu, H.; Wang, L. ARID1A recruits GATA2 to regulate the senescence of trophoblast cells under high-glucose condition. Placenta 2024, 158, 156–164. [Google Scholar] [CrossRef] [PubMed]
- Nelissen, E.C.; van Montfoort, A.P.; Dumoulin, J.C.; Evers, J.L. Epigenetics and the placenta. Hum. Reprod. Update 2011, 17, 397–417. [Google Scholar] [CrossRef] [PubMed]
- Fowden, A.L.; Coan, P.M.; Angiolini, E.; Burton, G.J.; Constancia, M. Imprinted genes and the epigenetic regulation of placental phenotype. Prog. Biophys. Mol. Biol. 2011, 106, 281–8. [Google Scholar] [CrossRef] [PubMed]
- Koukoura, O.; Sifakis, S.; Spandidos, D.A. DNA methylation in the human placenta and fetal growth (review). Mol. Med. Rep. 2012, 5, 883–9. [Google Scholar] [CrossRef] [PubMed]
- Xiao, X.; Zhao, Y.; Jin, R.; Chen, J.; Wang, X.; Baccarelli, A.; Zhang, Y. Fetal growth restriction and methylation of growth-related genes in the placenta. Epigenomics 2016, 8, 33–42. [Google Scholar] [CrossRef] [PubMed]
- Bednarek-Jędrzejek, M.; Taryma-Leśniak, O.; Poniatowska, M.; Cejko, M.; Maksym, K.; Dzidek, S.; Blatkiewicz, M.; Kwiatkowska, E.; Torbé, A.; Kwiatkowski, S. Integrative Analysis of Placental Methylomes Identifies Epigenetically Regulated Genes Implicated in Fetal Growth Restriction. Int. J. Mol. Sci. 2026, 27, 1448. [Google Scholar] [CrossRef] [PubMed]
- Koukoura, O.; Sifakis, S.; Soufla, G.; Zaravinos, A.; Apostolidou, S.; Jones, A.; Widschwendter, M.; Spandidos, D.A. Loss of imprinting and aberrant methylation of IGF2 in placentas from pregnancies complicated with fetal growth restriction. Int. J. Mol. Med. 2011, 28, 481–7. [Google Scholar] [CrossRef] [PubMed]
- Paauw, N.D.; Lely, A.T.; Joles, J.A.; Franx, A.; Nikkels, P.G.; Mokry, M.; van Rijn, B.B. H3K27 acetylation and gene expression analysis reveals differences in placental chromatin activity in fetal growth restriction. Clin. Epigenet. 2018, 10, 85. [Google Scholar] [CrossRef] [PubMed]
- Ma, X.; Chen, X.; Mu, X.; Cao, M.; Zhang, Y. Epigenetics of maternal-fetal interface immune microenvironment and placental related pregnancy complications. Front Immunol. 2025, 16, 1549839. [Google Scholar] [CrossRef] [PubMed]
- Fantone, S.; Mazzucchelli, R.; Giannubilo, S.R.; Ciavattini, A.; Marzioni, D.; Tossetta, G. AT-rich interactive domain 1A protein expression in normal and pathological pregnancies complicated by preeclampsia. Histochem Cell Biol. 2020, 154, 339–346. [Google Scholar] [CrossRef] [PubMed]
- Jin, M.; Xu, S.; Li, J.; Li, L.; Tang, C. Role of ARID1A in the Regulation of Human Trophoblast Migration and Invasion. Reprod. Sci. 2022, 29, 2363–2373. [Google Scholar] [CrossRef] [PubMed]
- Bi, Y.; Yang, J.; Hu, Y.; Lin, Y.; Gao, L.; Lv, J.; Wang, Y. Placental epigenetic and transcriptional dysregulation in type I selective fetal growth restriction. Placenta 2025, 168, 268–275. [Google Scholar] [CrossRef] [PubMed]
- Papuchova, H.; Lackner, A.; Vcelkova, T.; Tolp, P.; Haider, S.; Gerakopoulos, V.; Latos, P.A. Activity of the SWI/SNF complex is indispensable for syncytiotrophoblast formation. Development 2025, 152, dev204770. [Google Scholar] [CrossRef] [PubMed]
- Farrokhnia, F.; Aplin, J.D.; Westwood, M.; Forbes, K. MicroRNA regulation of mitogenic signaling networks in the human placenta. J. Biol. Chem. 2014, 289, 30404–30416. [Google Scholar] [CrossRef] [PubMed]
- Thamotharan, S.; Chu, A.; Kempf, K.; Janzen, C.; Grogan, T.; Elashoff, D.A.; Devaskar, S.U. Differential microRNA expression in human placentas of term intra-uterine growth restriction that regulates target genes mediating angiogenesis and amino acid transport. PLoS ONE 2017, 12, e0176493. [Google Scholar] [CrossRef] [PubMed]
- Wen, H.; Chen, L.; He, J.; Lin, J. MicroRNA expression profiles and networks in placentas complicated with selective intrauterine growth restriction. Mol. Med. Rep. 2017, 16, 6650–6673. [Google Scholar] [CrossRef] [PubMed]
- Xia, S.; Ye, Y.; Liu, J.; Qiu, H.; Lin, M.; He, Z.; Huang, L.; Wang, M.; Luo, Y. The Role of MALAT1 in Regulating the Proangiogenic Functions, Invasion, and Migration of Trophoblasts in Selective Fetal Growth Restriction. Biomolecules 2024, 14, 988. [Google Scholar] [CrossRef] [PubMed]
- Tsunoda, Y.; Kudo, M.; Wada, R.; Ishino, K.; Kure, S.; Sakatani, T.; Takeshita, T.; Naito, Z. Expression level of long noncoding RNA H19 of normotensive placentas in late pregnancy relates to the fetal growth restriction. J. Obstet. Gynaecol. Res. 2020, 46, 1025–1034. [Google Scholar] [CrossRef] [PubMed]
- Roos, S.; Jansson, N.; Palmberg, I.; Säljö, K.; Powell, T.L.; Jansson, T. Mammalian target of rapamycin in the human placenta regulates leucine transport and is down-regulated in restricted fetal growth. J. Physiol. 2007, 582, 449–59. [Google Scholar] [CrossRef]
- Rosario, F.J.; Dimasuay, K.G.; Kanai, Y.; Powell, T.L.; Jansson, T. Regulation of amino acid transporter trafficking by mTORC1 in primary human trophoblast cells is mediated by the ubiquitin ligase Nedd4-2. Clin. Sci. (Lond) 2016, 130, 499–512. [Google Scholar] [CrossRef] [PubMed]
- Gaccioli, F.; Lager, S. Placental Nutrient Transport and Intrauterine Growth Restriction. Front Physiol. 2016, 7, 40. [Google Scholar] [CrossRef] [PubMed]
- Glazier, J.D.; Cetin, I.; Perugino, G.; Ronzoni, S.; Grey, A.M.; Mahendran, D.; Marconi, A.M.; Pardi, G.; Sibley, C.P. Association between the activity of the system A amino acid transporter in the microvillous plasma membrane of the human placenta and severity of fetal compromise in intrauterine growth restriction. Pediatr. Res. 1997, 42, 514–9. [Google Scholar] [CrossRef] [PubMed]
- Avagliano, L.; Garò, C.; Marconi, A.M. Placental amino acids transport in intrauterine growth restriction. J. Pregnancy 2012, 2012, 972562. [Google Scholar] [CrossRef] [PubMed]
- Jansson, T.; Ylvén, K.; Wennergren, M.; Powell, T.L. Glucose transport and system A activity in syncytiotrophoblast microvillous and basal plasma membranes in intrauterine growth restriction. Placenta 2002, 23, 392–9. [Google Scholar] [CrossRef] [PubMed]
- Mandò, C.; Tabano, S.; Pileri, P.; Colapietro, P.; Marino, M.A.; Avagliano, L.; Doi, P.; Bulfamante, G.; Miozzo, M.; Cetin, I. SNAT2 expression and regulation in human growth-restricted placentas. Pediatr. Res. 2013, 74, 104–10. [Google Scholar] [CrossRef] [PubMed]
- Rosario, F.J.; Kanai, Y.; Powell, T.L.; Jansson, T. Mammalian target of rapamycin signalling modulates amino acid uptake by regulating transporter cell surface abundance in primary human trophoblast cells. J. Physiol. 2013, 591, 609–25. [Google Scholar] [CrossRef] [PubMed]
- Chen, Y.Y.; Rosario, F.J.; Shehab, M.A.; Powell, T.L.; Gupta, M.B.; Jansson, T. Increased ubiquitination and reduced plasma membrane trafficking of placental amino acid transporter SNAT-2 in human IUGR. Clin. Sci. (Lond) 2015, 129, 1131–41. [Google Scholar] [CrossRef] [PubMed]
- Shimada, H.; Powell, T.L.; Jansson, T. Regulation of placental amino acid transport in health and disease. Acta Physiol. (Oxf) 2024, 240, e14157. [Google Scholar] [CrossRef]
- Jansson, T.; Castillo-Castrejon, M.; Gupta, M.B.; Powell, T.L.; Rosario, F.J. Down-regulation of placental Cdc42 and Rac1 links mTORC2 inhibition to decreased trophoblast amino acid transport in human intrauterine growth restriction. Clin. Sci. (Lond) 2020, 134, 53–70. [Google Scholar] [CrossRef] [PubMed]
- Roos, S.; Kanai, Y.; Prasad, P.D.; Powell, T.L.; Jansson, T. Regulation of placental amino acid transporter activity by mammalian target of rapamycin. Am. J. Physiol. Cell Physiol. 2009, 296, C142–C150. [Google Scholar] [CrossRef] [PubMed]
- Chen, Y.Y.; Rosario, F.J.; Shehab, M.A.; Powell, T.L.; Gupta, M.B.; Jansson, T. Increased ubiquitination and reduced plasma membrane trafficking of placental amino acid transporter SNAT-2 in human IUGR. Clin. Sci. (Lond) 2015, 129, 1131–41. [Google Scholar] [CrossRef] [PubMed]
- Cleal, J.K.; Lofthouse, E.M.; Sengers, B.G.; Lewis, R.M. A systems perspective on placental amino acid transport. J. Physiol. 2018, 596, 5511–5522. [Google Scholar] [CrossRef] [PubMed]
- Lager, S.; Powell, T.L. Regulation of Nutrient Transport across the Placenta. J. Pregnancy 2012, 2012, 179827, 14 pages. [Google Scholar] [CrossRef] [PubMed]
- Illsley, N.P.; Baumann, Marc U. Human placental glucose transport in fetoplacental growth and metabolism. Biochim. Biophys. Acta-Mol. Basis Dis. 2020, 1866, 165359. [Google Scholar] [CrossRef] [PubMed]
- Hay, W.W., Jr. Placental-fetal glucose exchange and fetal glucose metabolism. Trans. Am. Clin. Climatol. Assoc. 2006, 117, 321-39; discussion 339-40. [Google Scholar] [PubMed]
- Illsley, N.P. Glucose transporters in the human placenta. Placenta 2000, 21, 14–22. [Google Scholar] [CrossRef] [PubMed]
- Janzen, C.; Lei, M.Y.; Cho, J.; Sullivan, P.; Shin, B.C.; Devaskar, S.U. Placental glucose transporter 3 (GLUT3) is up-regulated in human pregnancies complicated by late-onset intrauterine growth restriction. Placenta 2013, 34, 1072–8. [Google Scholar] [CrossRef] [PubMed]
- Brooker, I.A.; Fisher, J.J.; Sutherland, J.M.; Pringle, K.G. Understanding the impact of placental oxidative and nitrative stress in pregnancies complicated by fetal growth restriction. Placenta 2024, 158, 318–328. [Google Scholar] [CrossRef] [PubMed]
- Jones, H.N.; Powell, T.L.; Jansson, T. Regulation of placental nutrient transport--a review. Placenta 2007, 28, 763–74. [Google Scholar] [CrossRef] [PubMed]
- Hart, B.; Morgan, E.; Alejandro, E.U. Nutrient sensor signaling pathways and cellular stress in fetal growth restriction. J. Mol. Endocrinol. 2019, 62, R155–R165. [Google Scholar] [CrossRef] [PubMed]
- Wilson, S.L.; Robinson, W.P. Utility of DNA methylation to assess placental health. Placenta 2018, 64 Suppl 1, S23–S28. [Google Scholar] [CrossRef] [PubMed]
- He, L.; Hong, D.; Chen, H.; Chen, X. Placental dysfunction drives fetal growth restriction: mechanisms and translational perspectives. Front Mol. Biosci. 2026, 13, 1847608. [Google Scholar] [CrossRef] [PubMed]
- Burton, G.J.; Jauniaux, E. Pathophysiology of placental-derived fetal growth restriction. Am. J. Obstet. Gynecol. 2018, 218, S745–S761. [Google Scholar] [CrossRef] [PubMed]
- Smith, S.; Smith, J.; Jones, K.; Castillo, A.; Wiemann, N.; Howard, A.; Cunningham, M. Placental ischemia during pregnancy induces hypertension, cerebral inflammation, in dams postpartum. Hypertens. Pregnancy 2025, 44. [Google Scholar] [CrossRef] [PubMed]
- Chen, H.; Chen, Y.; Zheng, Q. The regulated cell death at the maternal-fetal interface: beneficial or detrimental? Cell Death Discov. 2024, 10, 100. [Google Scholar] [CrossRef] [PubMed]
- Ziganshina, M.M.; Krechetova, L.V.; Vanko, L.V.; Khodzhaeva, Z.S.; Yarotskaya, E.L.; Sukhikh, G.T. Angiogenesis-Related Factors in Early Pregnancy Loss [Internet]. Physiologic and Pathologic Angiogenesis - Signaling Mechanisms and Targeted Therapy; InTech, 2017. [Google Scholar] [CrossRef] [PubMed]
- Lockwood, C.J.; Oner, C.; Uz, Y.H.; Kayisli, U.A.; Huang, S.J.; Buchwalder, L.F.; Murk, W.; Funai, E.F.; Schatz, F. Matrix metalloproteinase 9 (MMP9) expression in preeclamptic decidua and MMP9 induction by tumor necrosis factor alpha and interleukin 1 beta in human first trimester decidual cells. Biol. Reprod. 2008, 78, 1064–72. [Google Scholar] [CrossRef] [PubMed]
- Colson, A.; Sonveaux, P.; Debiève, F.; Sferruzzi-Perri, A.N. Adaptations of the human placenta to hypoxia: opportunities for interventions in fetal growth restriction. Hum. Reprod. Update 2021, 27, 531–569. [Google Scholar] [CrossRef] [PubMed]
- Benton, S.J.; Hu, Y.; Xie, F.; Kupfer, K.; Lee, S.W.; Magee, L.A.; von Dadelszen, P. Can placental growth factor in maternal circulation identify fetuses with placental intrauterine growth restriction? Am. J. Obstet. Gynecol. 2012, 206, 163.e1–7. [Google Scholar] [CrossRef] [PubMed]
- Straszewski-Chavez, S.L.; Abrahams, V.M.; Funai, E.F.; Mor, G. X-linked inhibitor of apoptosis (XIAP) confers human trophoblast cell resistance to Fas-mediated apoptosis. Mol. Hum. Reprod. 2004, 10, 33–41. [Google Scholar] [CrossRef] [PubMed]
- Arroyo, J.; Price, M.; Straszewski-Chavez, S.; Torry, R. J.; Mor, G.; Torry, D. S. XIAP protein is induced by placenta growth factor (PLGF) and decreased during preeclampsia in trophoblast cells. Syst. Biol. Reprod. Med. 2014, 60, 263–273. [Google Scholar] [CrossRef] [PubMed]
- Vaughan, O.; Fowden, A. Placental metabolism: substrate requirements and the response to stress. Reprod. Dom. Anim. 2016, 51, 25–35. [Google Scholar] [CrossRef] [PubMed]
- Illsley, N.P.; Baumann, M.U. Human placental glucose transport in fetoplacental growth and metabolism. Biochim Biophys. Acta Mol. Basis Dis. 2020, 1866, 165359. [Google Scholar] [CrossRef] [PubMed]
- Hung, T.H.; Wu, C.P.; Chen, S.F. Differential Changes in Akt and AMPK Phosphorylation Regulating mTOR Activity in the Placentas of Pregnancies Complicated by Fetal Growth Restriction and Gestational Diabetes Mellitus With Large-For-Gestational Age Infants. Front Med. 2021, 8, 788969. [Google Scholar] [CrossRef] [PubMed]
- Francis, E.C.; Shimada, H.; Powell, T.L.; et al. Normalization of trophoblast mTOR signaling rescues impaired function in primary human trophoblast cells isolated from pregnancies complicated by fetal growth restriction. Cell Death Discov. 2025, 11, 513. [Google Scholar] [CrossRef] [PubMed]
- Xu, Q.; Wang, J.; Li, Y.; Lei, H.; Jin, N.; Lu, J.; Qian, C.; Zhang, J.; Dong, J.; Wang, X. The inhibition of placental mTOR signaling leads to fetal growth restriction with abnormal glucose metabolism in different anatomical regions of placentas. Placenta 2025, 164, 31–40. [Google Scholar] [CrossRef] [PubMed]
- Banister, C.E.; Koestler, D.C.; Maccani, M.A.; Padbury, J.F.; Houseman, E.A.; Marsit, C.J. Infant growth restriction is associated with distinct patterns of DNA methylation in human placentas. Epigenetics 2011, 6, 920–7. [Google Scholar] [CrossRef] [PubMed]
- Bourque, D.K.; Avila, L.; Peñaherrera, M.; von Dadelszen, P.; Robinson, W.P. Decreased placental methylation at the H19/IGF2 imprinting control region is associated with normotensive intrauterine growth restriction but not preeclampsia. Placenta 2010, 31, 197–202. [Google Scholar] [CrossRef] [PubMed]
- Bi, Y.; Yang, J.; Hu, Y.; Lin, Y.; Gao, L.; Lv, J.; Wang, Y. Placental epigenetic and transcriptional dysregulation in type I selective fetal growth restriction. Placenta 2025, 168, 268–275. [Google Scholar] [CrossRef] [PubMed]
- Huang, B.; Wang, H.; An, Z.; Yang, Z.; Cao, J.; Wang, L.; Luo, X.; Qi, H. Compromised Peroxisome Proliferator-Activated Receptor γ-Mediated Impaired Placental Glucose Transport Via the Phosphatidylinositol 3-Kinase/Protein Kinase B Signaling Pathway Is Associated With Fetal Growth Restriction. Lab Invest. 2025, 105, 104103. [Google Scholar] [CrossRef] [PubMed]
- Yang, G.; Wang, N.; Liu, H.; Si, L.; Zhao, Y. The association between umbilical cord blood fat-soluble vitamin concentrations and infant birth weight. Front Endocrinol. 2023, 14, 1048615. [Google Scholar] [CrossRef] [PubMed]
- Kochhar, P.; Vukku, M.; Rajashekhar, R.; Mukhopadhyay, A. microRNA signatures associated with fetal growth restriction: a systematic review. Eur. J. Clin. Nutr. 2022, 76, 1088–1102. [Google Scholar] [CrossRef] [PubMed]
- Krishnan, T.; David, A.L. Placenta-directed gene therapy for fetal growth restriction. Semin Fetal Neonatal Med. 2017, 22, 415–422. [Google Scholar] [CrossRef] [PubMed]
- Sharp, A.; Cornforth, C.; Jackson, R.; Harrold, J.; Turner, M.A.; Kenny, L.; Baker, P.N.; Johnstone, E.D.; Khalil, A.; von Dadelszen, P.; Papageorghiou, A.T.; Vollmer, B.; Alfirevic, Z. The efficacy of sildenafil therapy in dismal prognosis early-onset intrauterine growth restriction: the STRIDER RCT; National Institute for Health and Care Research: Southampton (UK), Oct 2024. [Google Scholar]
- Rock, C.R.; Miller, S.L.; Allison, B.J. The Use of Antioxidants for Cardiovascular Protection in Fetal Growth Restriction: A Systematic Review. Antioxidants 2024, 13, 1400. [Google Scholar] [CrossRef] [PubMed]
- Lees, C.C.; Romero, R.; Stampalija, T.; Dall'Asta, A.; DeVore, G.A.; Prefumo, F.; Frusca, T.; Visser, G.H.A.; Hobbins, J.C.; Baschat, A.A.; Bilardo, C.M.; Galan, H.L.; Campbell, S.; Maulik, D.; Figueras, F.; Lee, W.; Unterscheider, J.; Valensise, H.; Da Silva Costa, F.; Salomon, L.J.; Poon, L.C.; Ferrazzi, E.; Mari, G.; Rizzo, G.; Kingdom, J.C.; Kiserud, T.; Hecher, K. Clinical Opinion: The diagnosis and management of suspected fetal growth restriction: an evidence-based approach. Am. J. Obstet. Gynecol. 2022, 226, 366–378. [Google Scholar] [CrossRef] [PubMed]
- Villalaín, C.; Herraiz, I.; Akolekar, R.; Figueras, F.; Crispi, F.; Rizzo, G.; Mappa, I.; Mendoza, M.; Del Moral, T.; Stampalija, T.; Ghi, T.; Galindo, A. Clinical practice guidance for the management of fetal growth restriction: an expert review. J. Matern Fetal Neonatal Med. 2025, 38, 2526111. [Google Scholar] [CrossRef] [PubMed]
- Majumder, S.; Moriarty, K.L.; Lee, Y.; Crombleholme, T.M. Placental Gene Therapy for Fetal Growth Restriction and Preeclampsia: Preclinical Studies and Prospects for Clinical Application. J. Clin. Med. 2024, 13, 5647. [Google Scholar] [CrossRef] [PubMed]
- Zheng, S.; Georgiou, H.M.; Kokkinos, M.I.; Mirabito Colafella, K.M.; Brennecke, S.P.; Kalionis, B. Therapeutic potential of extracellular vesicles for treating human pregnancy disorders. Extracell. Vesicles Circ. Nucl. Acids 2025, 6, 287–309. [Google Scholar] [CrossRef] [PubMed]
- Nadel, A.; Prabhu, M.; Kaimal, A. Fetal Growth Restriction: A Pragmatic Approach. Am. J. Perinatol. 2025, 42, 1223–1228. [Google Scholar] [CrossRef] [PubMed]
- Kehl, S.; Bahlmann, F.; Dötsch, J.; Felderhoff-Müser, U.; Groten, T.; Manegold-Brauer, G.; Hecher, K.; Klaritsch, P.; Lobmaier, S.; Pecks, U.; Raio, L.; Schlembach, D.; Schmitz, D.; von Kaisenberg, C. Fetal Growth Restriction. Guideline of the DGGG, OEGGG and SGGG (S2k-Level, AWMF Registry No. 015/080, October 2024). Geburtshilfe Frauenheilkd. 2025, 85, 1033–1060. [Google Scholar] [CrossRef] [PubMed]
- Zhang, B.; Fan, X.; Nayak, N.R. Trophoblast-Targeted Liposomes for Placenta-Specific Drug Delivery. Methods Mol. Biol. 2024, 2728, 173–180. [Google Scholar] [CrossRef] [PubMed]
- van Kammen, C.M.; van Woudenberg, S.J.; Schiffelers, R.; Terstappen, F.; Lely, A.T. Nanomedicines: An approach to treat placental insufficiency and the current challenges. J. Control Release 2023, 360, 57–68. [Google Scholar] [CrossRef] [PubMed]
- Deepak, V.; El-Balawi, L.; Harris, L.K. Placental Drug Delivery to Treat Pre-Eclampsia and Fetal Growth Restriction. Small 2024, 20, e2311165. [Google Scholar] [CrossRef] [PubMed]
- Geisler, H.C.; Ghalsasi, A.A.; Safford, H.C.; Swingle, K.L.; Thatte, A.S.; Mukalel, A.J.; Gong, N.; Hamilton, A.G.; Han, E.L.; Nachod, B.E.; Padilla, M.S.; Mitchell, M.J. EGFR-targeted ionizable lipid nanoparticles enhance in vivo mRNA delivery to the placenta. J. Control Release 2024, 371, 455–469. [Google Scholar] [CrossRef] [PubMed]
- Taglauer, E.S.; Fernandez-Gonzalez, A.; Willis, G.R.; Reis, M.; Yeung, V.; Liu, X.; Mitsialis, S.A.; Kourembanas, S. Mesenchymal stromal cell-derived extracellular vesicle therapy prevents preeclamptic physiology through intrauterine immunomodulation†. Biol. Reprod. 2021, 104, 457–467. [Google Scholar] [CrossRef] [PubMed]
- Zheng, S.; Georgiou, H.M.; Kokkinos, M.I.; Mirabito Colafella, K.M.; Brennecke, S.P.; Kalionis, B. Therapeutic potential of extracellular vesicles for treating human pregnancy disorders. Extracell. Vesicles Circ. Nucl. Acids 2025, 6, 287–309. [Google Scholar] [CrossRef] [PubMed]
- Suvakov, S.; Richards, C.; Nikolic, V.; Simic, T.; McGrath, K.; Krasnodembskaya, A.; McClements, L. Emerging Therapeutic Potential of Mesenchymal Stem/Stromal Cells in Preeclampsia. Curr. Hypertens. Rep. 2020, 22, 37. [Google Scholar] [CrossRef] [PubMed]
- King, A.; Ndifon, C.; Lui, S.; Widdows, K.; Kotamraju, V.R.; Agemy, L.; Teesalu, T.; Glazier, J.D.; Cellesi, F.; Tirelli, N.; Aplin, J.D.; Ruoslahti, E.; Harris, L.K. Tumor-homing peptides as tools for targeted delivery of payloads to the placenta. Sci. Adv. 2016, 2, e1600349. [Google Scholar] [CrossRef] [PubMed]
- Renshall, L.J.; Beards, F.; Evangelinos, A.; Greenwood, S.L.; Brownbill, P.; Stevens, A.; Sibley, C.P.; Aplin, J.D.; Johnstone, E.D.; Teesalu, T.; Harris, L.K. Targeted Delivery of Epidermal Growth Factor to the Human Placenta to Treat Fetal Growth Restriction. Pharmaceutics 2021, 13, 1778. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Schematic representation of the role of proinflammatory and anti-inflammatory cytokines in the regulation of placental function during normal pregnancy and the immune balance disorders that contribute to the pathogenesis of FGR; (abbreviations, IL-10: Ιnterleukin-10; TNF-α: Tumor necrosis factor-alpha; IL-1β: Interleukin-1 beta; IL-6: Interleukin-6; IL-8: Interleukin-8; IL-18: Interleukin-18; AGA: Appropriate for gestational age; FGR: Fetal growth restriction).
Figure 1.
Schematic representation of the role of proinflammatory and anti-inflammatory cytokines in the regulation of placental function during normal pregnancy and the immune balance disorders that contribute to the pathogenesis of FGR; (abbreviations, IL-10: Ιnterleukin-10; TNF-α: Tumor necrosis factor-alpha; IL-1β: Interleukin-1 beta; IL-6: Interleukin-6; IL-8: Interleukin-8; IL-18: Interleukin-18; AGA: Appropriate for gestational age; FGR: Fetal growth restriction).
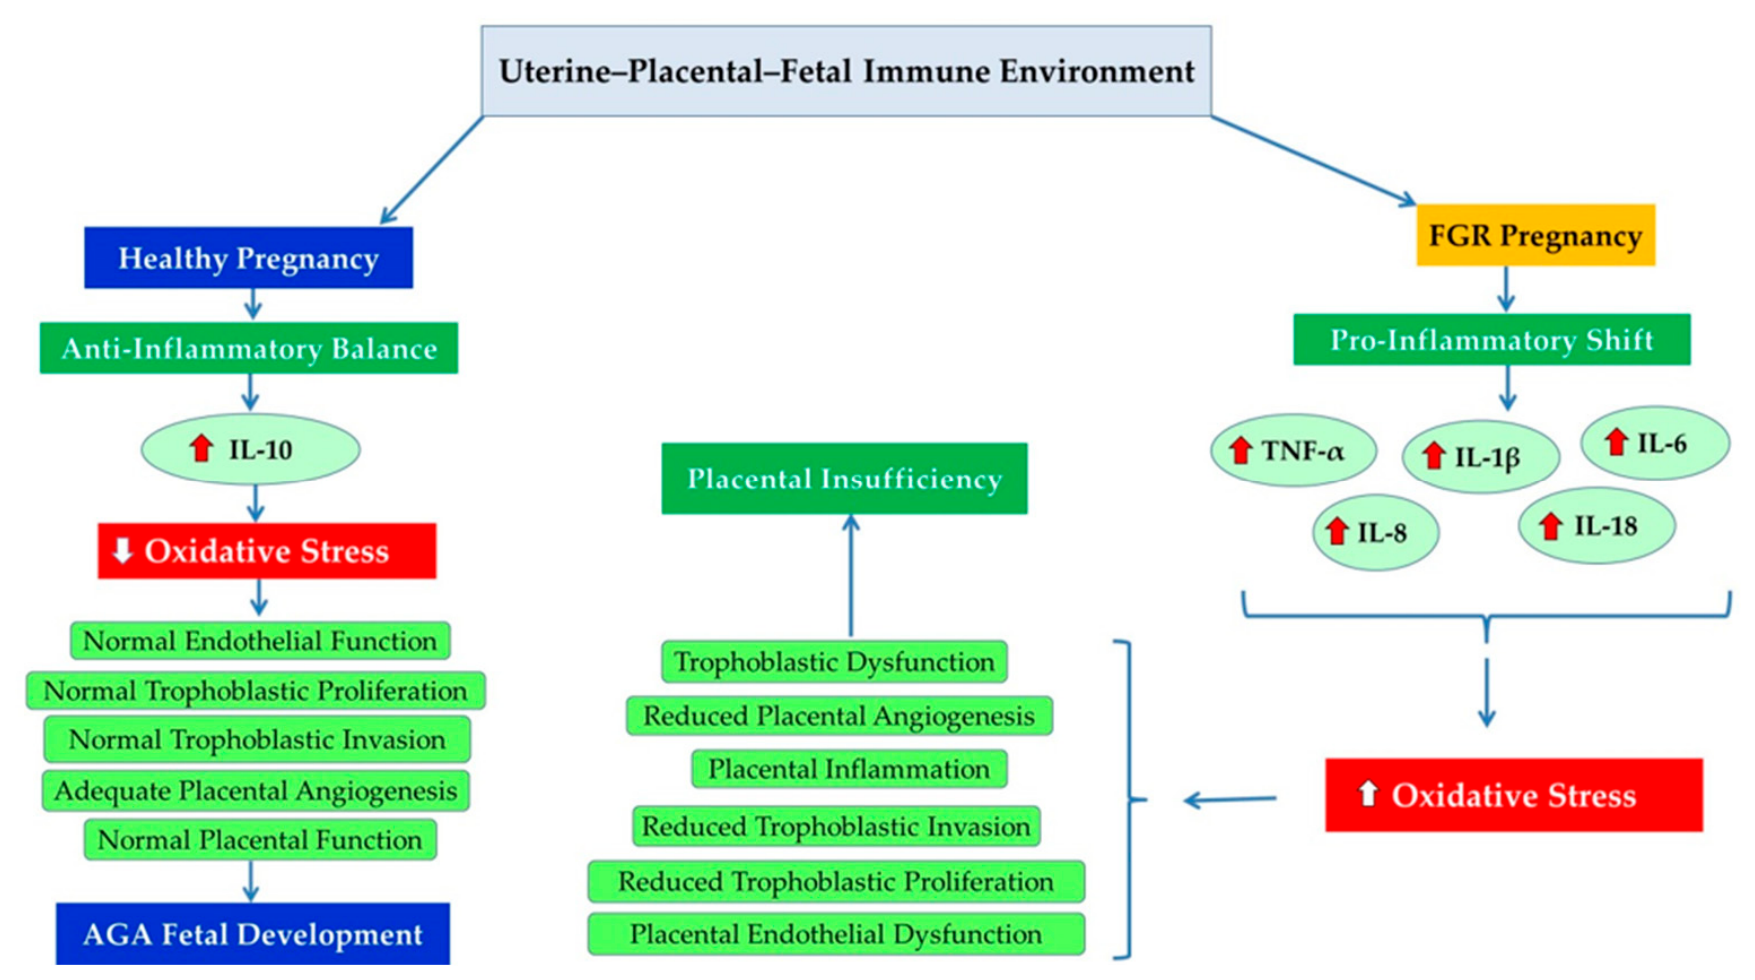
Figure 2.
Schematic representation of the imbalance between anti-inflammatory (adiponectin, apelin) and pro-inflammatory adipokines (leptin, visfatin, resistin, PAI-1, chemerin, FABP-4) and their contribution to the creation of a pro-inflammatory placental microenvironment in FGR; (abbreviations, PAI-1: Plasminogen Activator Inhibitor-1; FABP4: Fatty Acid Binding Protein 4; FGR: Fetal growth restriction).
Figure 2.
Schematic representation of the imbalance between anti-inflammatory (adiponectin, apelin) and pro-inflammatory adipokines (leptin, visfatin, resistin, PAI-1, chemerin, FABP-4) and their contribution to the creation of a pro-inflammatory placental microenvironment in FGR; (abbreviations, PAI-1: Plasminogen Activator Inhibitor-1; FABP4: Fatty Acid Binding Protein 4; FGR: Fetal growth restriction).
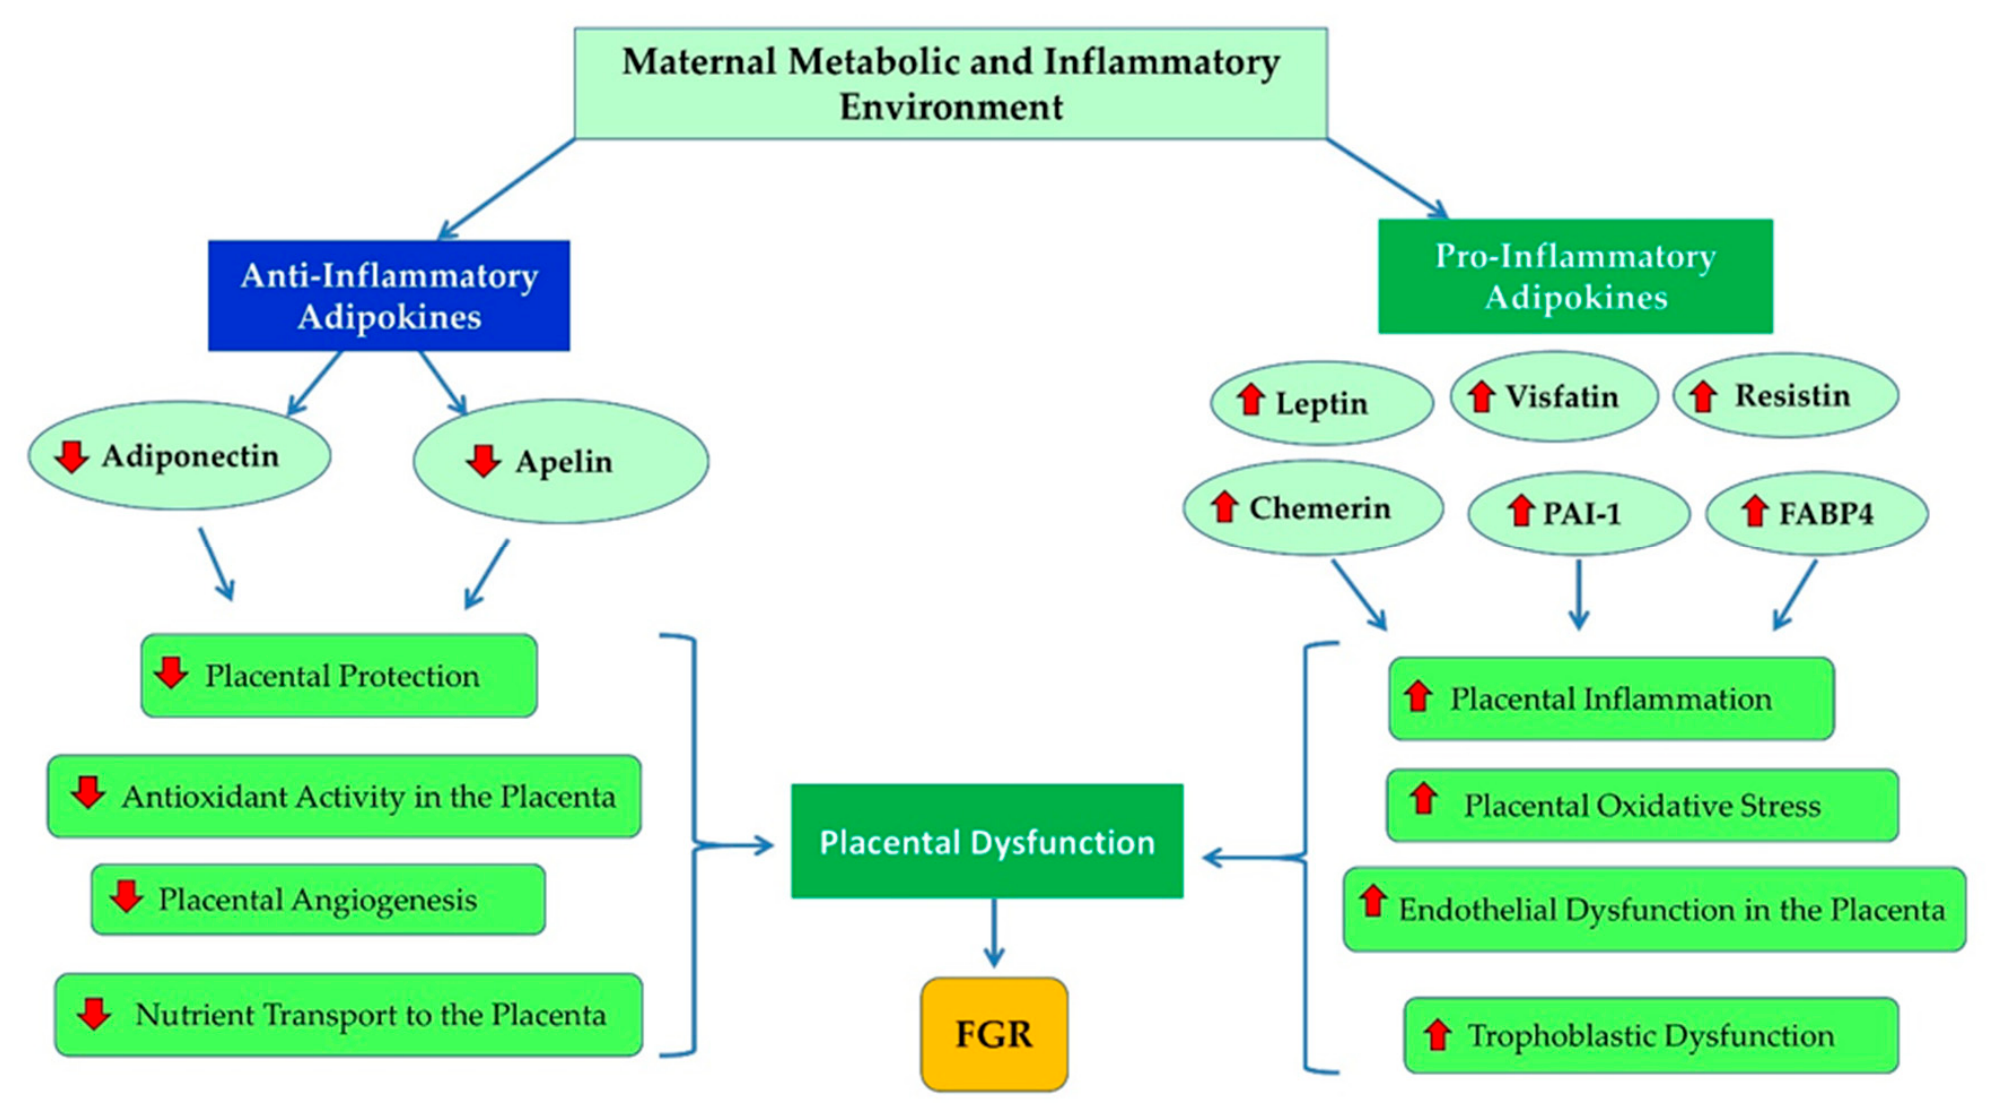
Figure 3.
Role of the NLRP3 inflammasome in the regulation of placental homeostasis during normal pregnancy and contribution of its hyperactivation to inflammation, trophoblastic pyrogenesis and the pathogenesis of FGR; (abbreviations, NLRP3: NOD-like receptor family pyrin domain containing 3; IL-1β: Interleukin-1β; IL-18: Interleukin-18; FGR: Fetal growth restriction).
Figure 3.
Role of the NLRP3 inflammasome in the regulation of placental homeostasis during normal pregnancy and contribution of its hyperactivation to inflammation, trophoblastic pyrogenesis and the pathogenesis of FGR; (abbreviations, NLRP3: NOD-like receptor family pyrin domain containing 3; IL-1β: Interleukin-1β; IL-18: Interleukin-18; FGR: Fetal growth restriction).
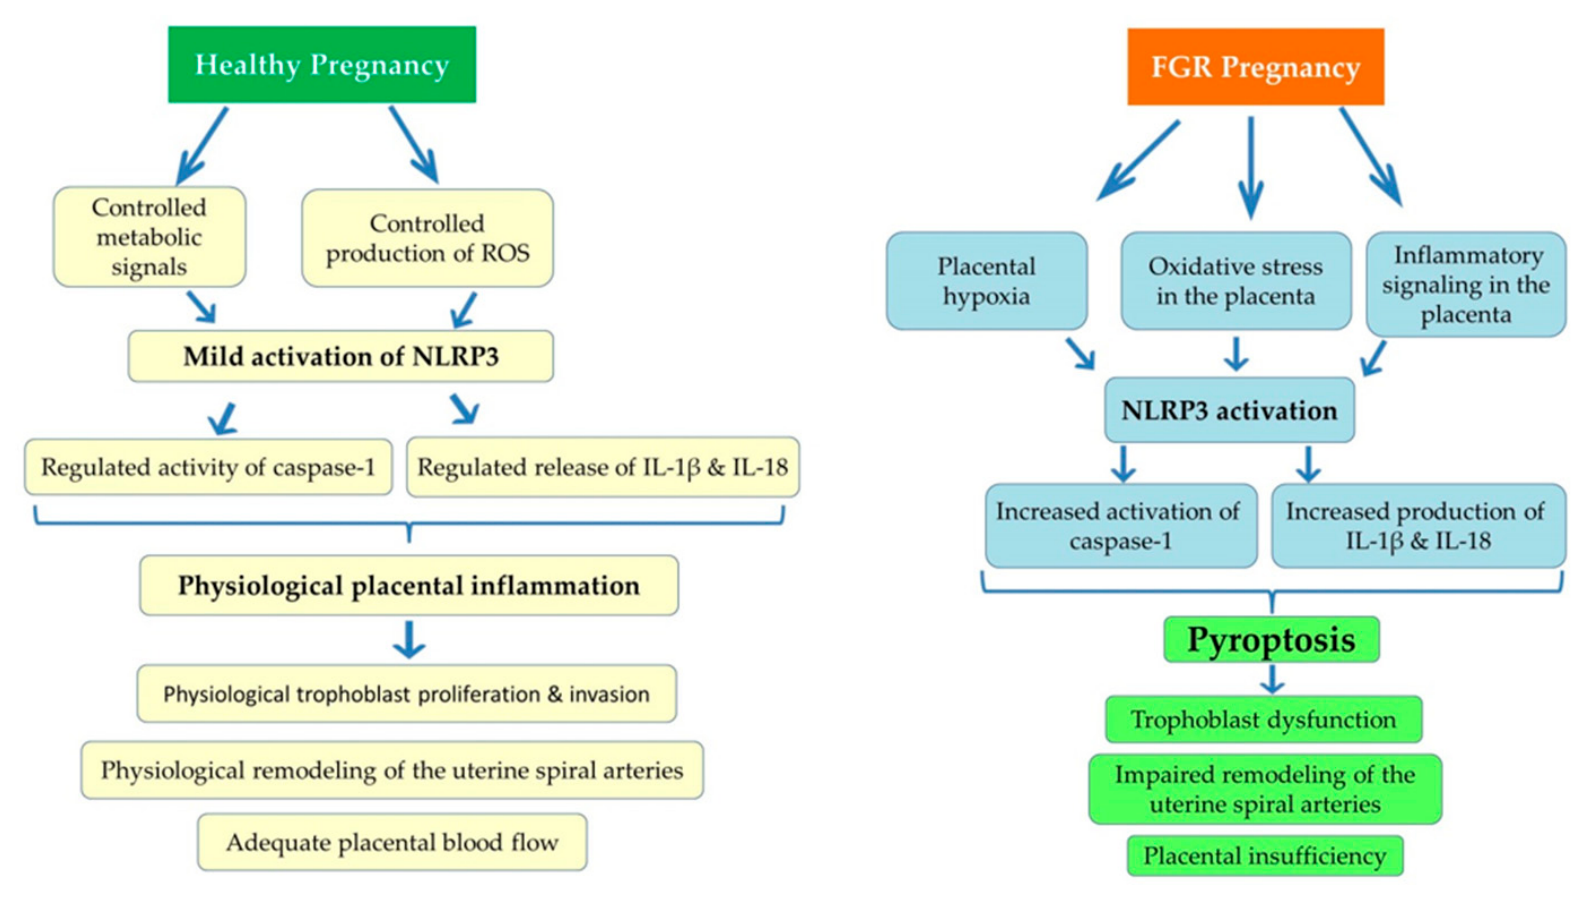
Figure 4.
Schematic illustration of the role of PlGF in healthty and FGR pregnancy; (abbreviations, PIGF: Placental growth factor; VEGFR-1: Vascular endothelial growth factor receptor 1; IGF-1: Insulin-like growth factor 1; FGR: Fetal growth restriction).
Figure 4.
Schematic illustration of the role of PlGF in healthty and FGR pregnancy; (abbreviations, PIGF: Placental growth factor; VEGFR-1: Vascular endothelial growth factor receptor 1; IGF-1: Insulin-like growth factor 1; FGR: Fetal growth restriction).
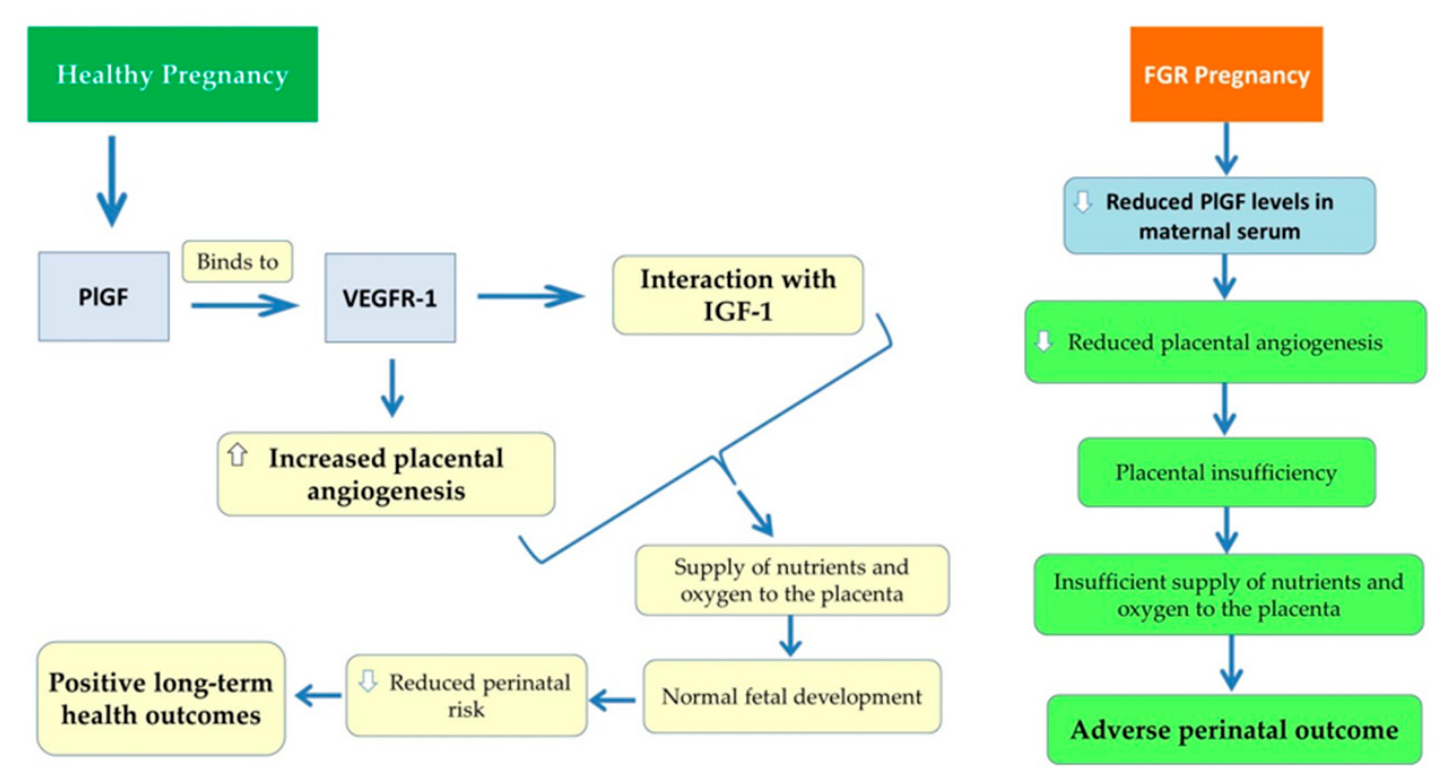
Figure 5.
Schematic illustration of the role of VEGF in healthy and FGR pregnancy; (abbreviation, VEGF: Vascular endothelial growth factor; VEGFR-1: Vascular endothelial growth factor receptor 1; VEGFR-2: Vascular endothelial growth factor receptor 2; sFlt-1: Soluble fms-like tyrosine kinase-1; AGA: Appropriate for Gestational Age; FGR: Fetal Growth Restriction).
Figure 5.
Schematic illustration of the role of VEGF in healthy and FGR pregnancy; (abbreviation, VEGF: Vascular endothelial growth factor; VEGFR-1: Vascular endothelial growth factor receptor 1; VEGFR-2: Vascular endothelial growth factor receptor 2; sFlt-1: Soluble fms-like tyrosine kinase-1; AGA: Appropriate for Gestational Age; FGR: Fetal Growth Restriction).
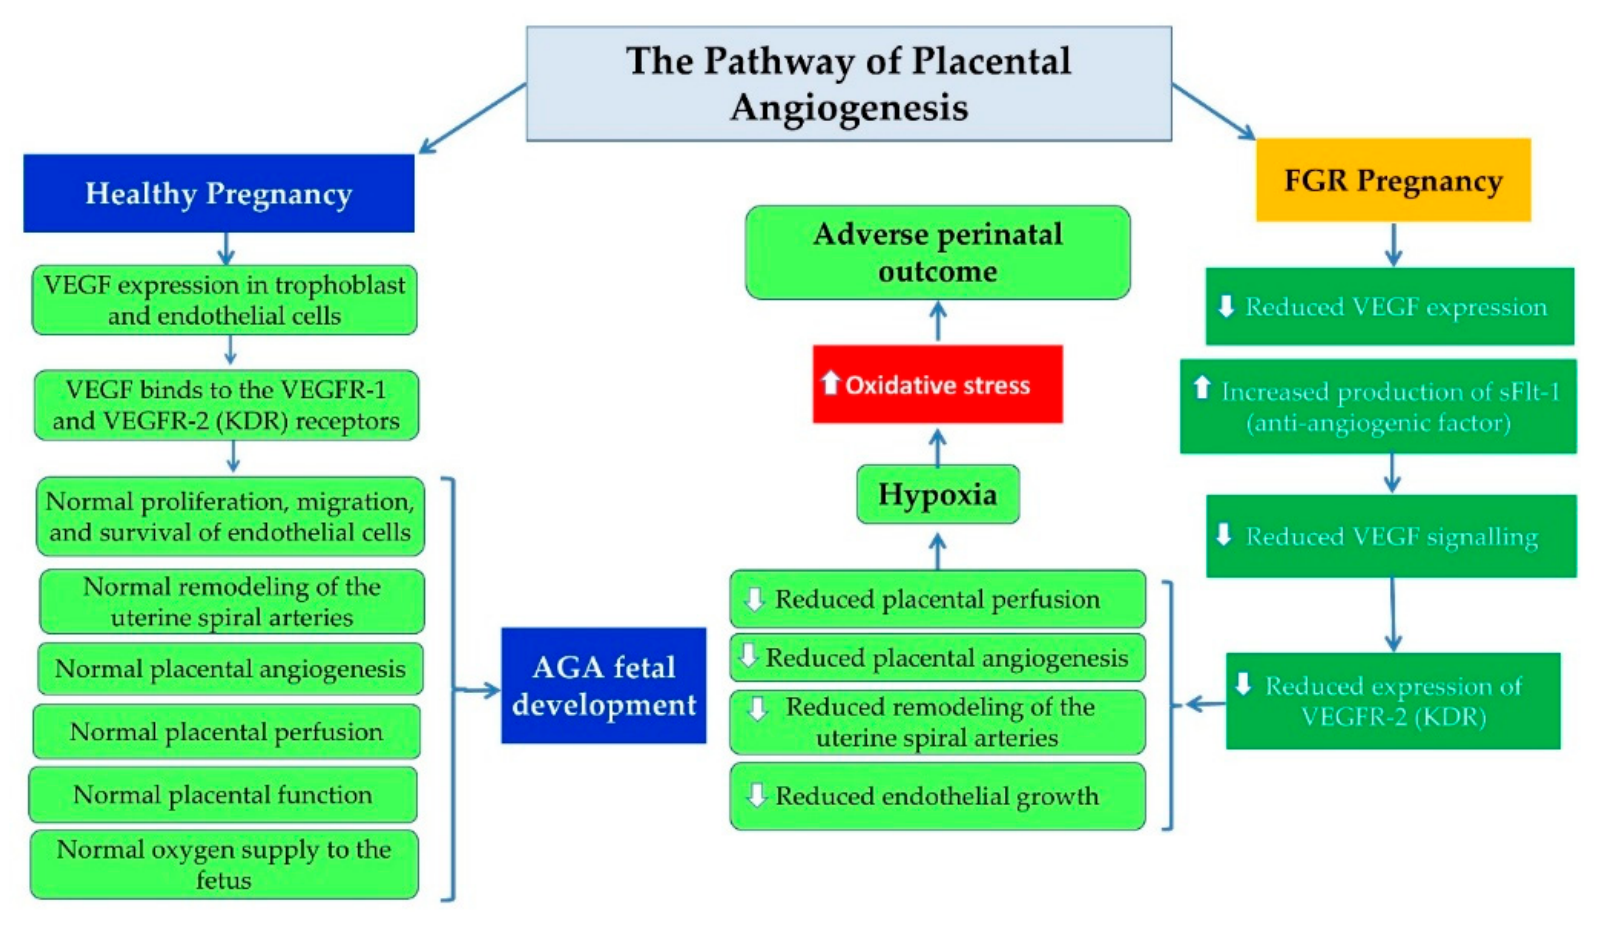
Figure 7.
Tumor suppressor and chromatin-regulatory pathways in FGR. Schematic illustration of the interconnected molecular networks governing placental development and fetal growth. The left panel outlines the pathological hyperactivation or dysfunction of key tumor suppressor pathways, where p53 induction promotes cell-cycle arrest and apoptosis, PTEN upregulation constrains downstream PI3K/Akt/mTOR signaling to decrease survival, and ARID1A loss disrupts trophoblast differentiation and motile capacity. The right panel represents the corresponding layers of chromatin-regulatory pathways, including promoter hypermethylation, altered histone acetylation/methylation, impaired SWI/SNF (SNF2H/BRG1) nucleosome positioning, and post-transcriptional microRNA/lncRNA networks. The convergence of these upstream epigenetic and genomic alterations compromises the maternal-fetal interface, driving impaired trophoblast invasion, defective angiogenesis, accelerated cell death, and blunted nutrient transporter trafficking, which collectively culminate in placental vascular dysfunction and FGR.
Figure 7.
Tumor suppressor and chromatin-regulatory pathways in FGR. Schematic illustration of the interconnected molecular networks governing placental development and fetal growth. The left panel outlines the pathological hyperactivation or dysfunction of key tumor suppressor pathways, where p53 induction promotes cell-cycle arrest and apoptosis, PTEN upregulation constrains downstream PI3K/Akt/mTOR signaling to decrease survival, and ARID1A loss disrupts trophoblast differentiation and motile capacity. The right panel represents the corresponding layers of chromatin-regulatory pathways, including promoter hypermethylation, altered histone acetylation/methylation, impaired SWI/SNF (SNF2H/BRG1) nucleosome positioning, and post-transcriptional microRNA/lncRNA networks. The convergence of these upstream epigenetic and genomic alterations compromises the maternal-fetal interface, driving impaired trophoblast invasion, defective angiogenesis, accelerated cell death, and blunted nutrient transporter trafficking, which collectively culminate in placental vascular dysfunction and FGR.
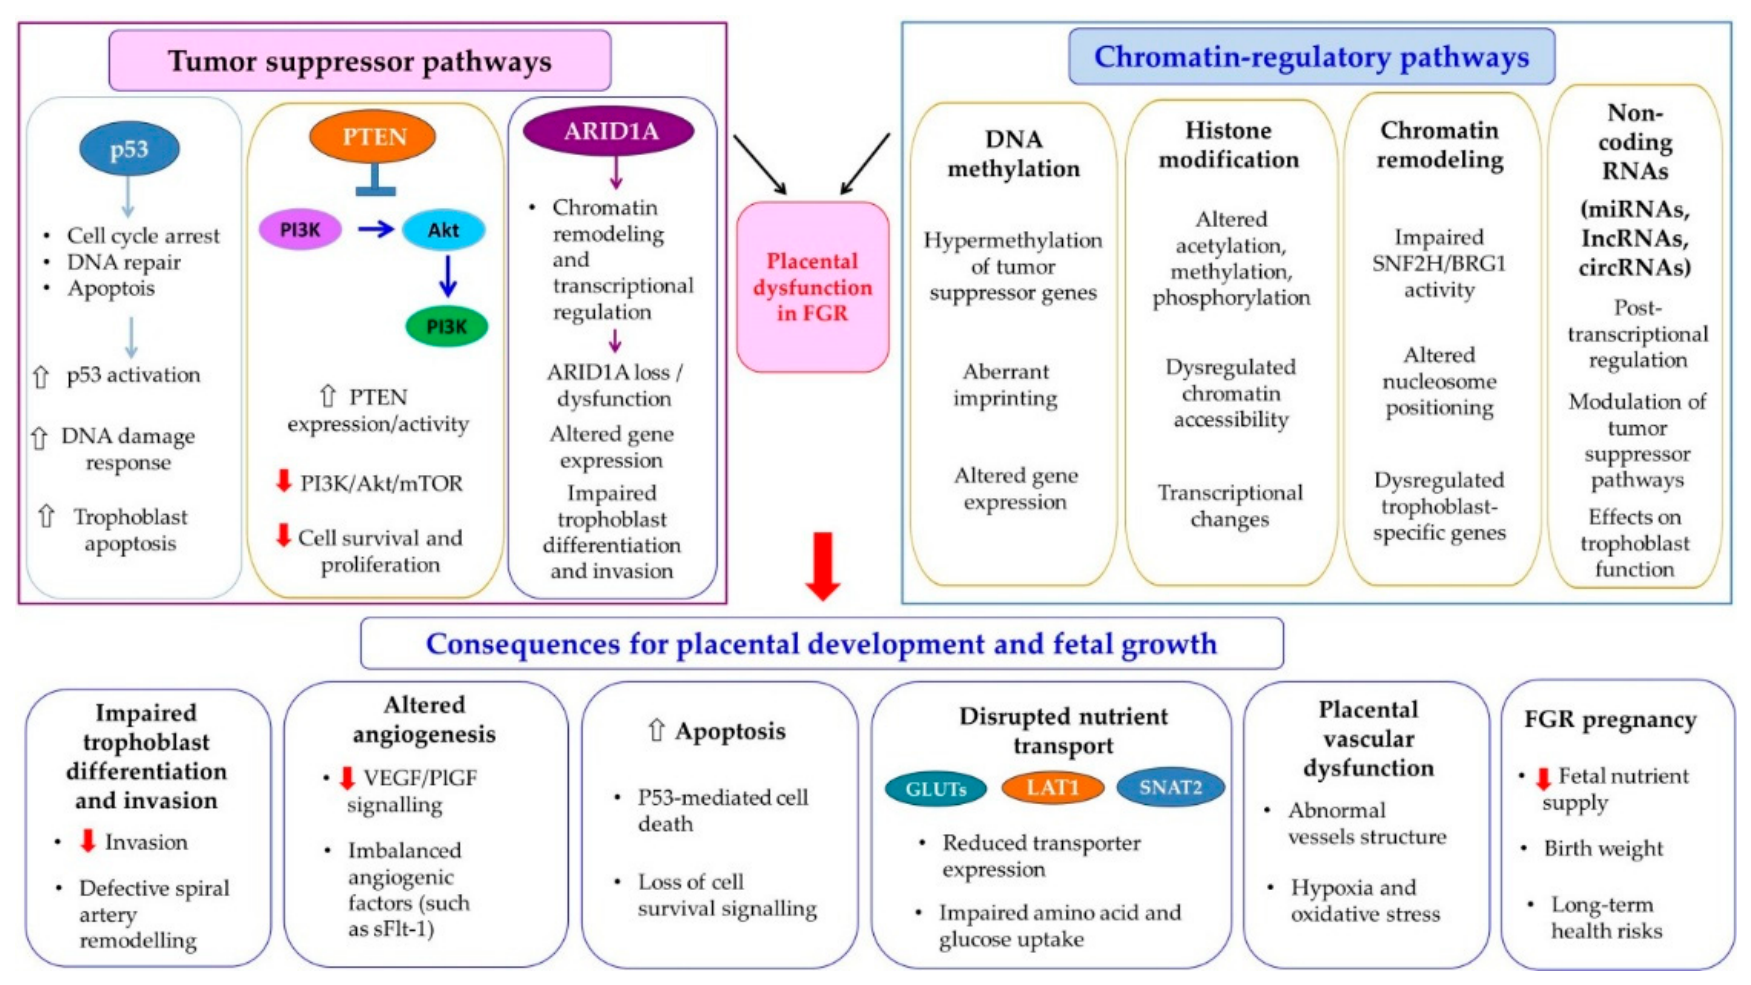
Figure 8.
Integrated molecular network linking placental dysfunction to FGR. The schematic illustrates the interconnected roles of inflammation, oxidative stress, extracellular-matrix remodeling, angiogenic imbalance, cellular senescence, survival signaling, mTOR-dependent nutrient sensing, and placental nutrient transport in the pathophysiology of FGR. The downstream consequences converge on impaired trophoblast function, defective maternal–fetal vascular adaptation, altered nutrient availability, and placental insufficiency, while spatial transcriptomics and single-cell epigenomics provide a framework for molecular stratification and the development of placenta-selective therapeutic strategies.
Figure 8.
Integrated molecular network linking placental dysfunction to FGR. The schematic illustrates the interconnected roles of inflammation, oxidative stress, extracellular-matrix remodeling, angiogenic imbalance, cellular senescence, survival signaling, mTOR-dependent nutrient sensing, and placental nutrient transport in the pathophysiology of FGR. The downstream consequences converge on impaired trophoblast function, defective maternal–fetal vascular adaptation, altered nutrient availability, and placental insufficiency, while spatial transcriptomics and single-cell epigenomics provide a framework for molecular stratification and the development of placenta-selective therapeutic strategies.
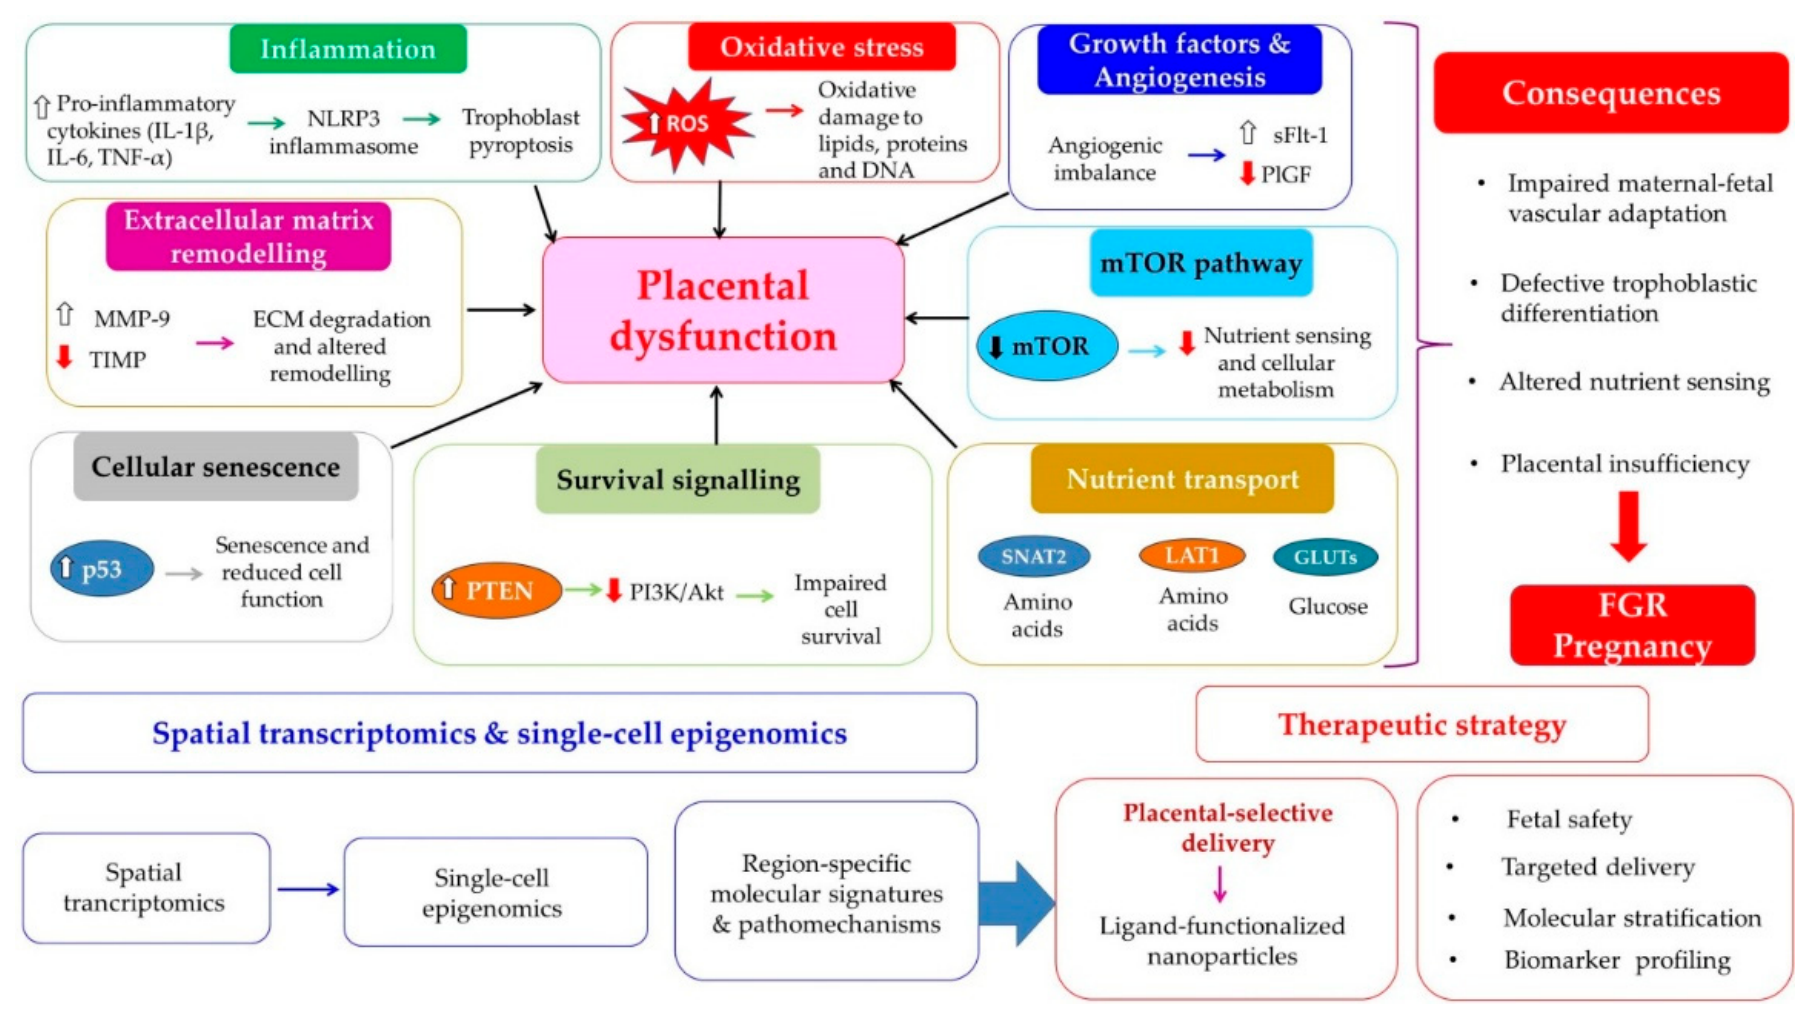

| Molecular Factor / Pathway | Principal Physiological role in the Placenta | Alterations Associated with FGR | Potential Contribution to Placental Dysfynction | Evidence in FGR (Placenta, Maternal Serum, Cord Blood) | Ref. |
|---|---|---|---|---|---|
| Inflammatory cytokines (IL-1β, IL-6, TNF-α) | Participate in controlled immune adaptation at the maternal-fetal interface. | Increased inflammatory signaling has been associated with placental dysfunction and FGR. | Chronic inflammation can impair trophoblast function, vascular remodeling and endothelial integrity. | Placenta: Evidence of increased inflammatory signaling. Maternal blood: Cytokine alterations have been reported in FGR, although results vary between studies. Cord blood: Inflammatory biomarkers may be altered, but findings are heterogenous. | [170] |
| Adipokines (adiponectin, apelin, leptin, visfatin, resistin, PAI-1, chemerin, FABP-4) | Regulate placental energy metabolism, nutrient transport, angiogenesis, endothelial and inflammatory homeostasis. | Reduced adiponectin and 26urviv; increased leptin, visfatin, resistin, PAI-1, chemerin and FABP-4 have been reported in FGR placental dysfunction. | A shift toward a pro-inflammatory, pro-oxidative adipokine profile may promote endothelial dysfunction, impaired placental signaling and inadequate fetal growth. | Placenta: Altered adipokines expression/concentration is reported. Maternal blood: Reduced adiponectin and apelin and increased pro-inflammatory adipokines have been reported. Cord blood: Alterations have also been described, but the evidence is less uniform than for maternal seruma and placenta. | [35,36,37,38] |
| NLRP3 Inflammasome | Innate immune multi-protein complex activating caspase-1 and maturation/secretion of IL-1β; participates in placental inflammatory homeostasis. | Increased placental NLRP3 activation, caspase-1, IL-1β and IL-18 are reported in FGR. | Promotes inflammatory signaling and trophoblast pyroptosis, with potential effects on proliferation, invasion and placental vascular remodeling. | Placenta: Increased NLRP3 inflammasome expression and activation have been demonstrated in FGR placental tissue, with increased NLRP3, caspase-1 and downstream inflammatory signaling. Maternal blood: Evidence for circulating NLRP3-related inflammatory changes in FGR is limited. Although inflammasome-associated markers and cytokines have been investigated in maternal blood, NLRP3 has not been established as a validated circulating biomarker of FGR. Cord blood: Direct evidence for NLRP3 inflammasome activation in cord blood from FGR pregnancies is limited. Alterations in inflammasome-related inflammatory mediators have been reported, but NLRP3 itself has not been sufficiently validated as a cord-blood biomarker of FGR. | [9] |
| MMP-9/TIMP System | Extracellular-matrix degradation and remodeling; supports extravillous trophoblast invasion, spiral-artery remodeling and angiogenic-factor modification. | Placental MMP-9 expression/activity may be reduced, whereas some studies report increased circulating MMP-9 in FGR. | Disturbed MMP-9/TIMP-1 activity may impair trophoblast invasion, extracellular-matrix turnover and spiral-artery remodeling. | Placenta: Human evidence of altered MMP-9 expression/activity in FGR. Maternal blood: Increased circulating MMP-9 has been reported in some FGR cohorts. Cord blood: Not established as a validated FGR biomarker. | [10,11,58] |
| VEGF / PlGF | Promote placental angiogenesis, endothelial proliferation and development of the villous vascular network. | Reduced pro-angiogenic activity and altered circulating concentrations, particularly of PlGF, are associated with placental insufficiency. | Impaired angiogenesis and endothelial function, contributing to inadequate uteroplacental perfusion. | Placenta: Altered angiogenic signaling documented. Maternal blood: Strong evidence for altered PlGF and VEGF-related angiogenic balance. Cord blood: Less consistently investigated as a clinical marker of FGR. | [12,14] |
| TGF-β signaling | Regulates trophoblast differentiation and invasion, extracellular matrix remodeling, immune adaptation and aspects of vascular development. | Altered TGF-β2 expression has been reported in placental and placental-bed tissues in FGR. | May contribute to abnormal trophoblast invasion, impaired spiral artery remodeling and altered placental architecture. | Placenta: Evidence of altered TGF-β2 expression/localization in FGR. Maternal blood: Limited direct evidence for TGF-β2 as an FGR biomarker. Cord blood: Evidence exists for TGF-β1, but this should not be extrapolated directly to TGF-β2. | [83] |
| IGF / IGFBP system | Regulates trophoblast proliferation, differentiation, survival, angiogenesis and nutrient transport; IGFBPs control IGF bioavailability. | Reduced IGF-1 and altered placental IGF-2/IGFBP expression have been reported in FGR; IGFBP-1/2 may increase while IGFBP-3 may decrease. | Reduced IGF bioactivity may impair trophoblast growth, increase apoptosis, disturb angiogenesis and reduce nutrient transport. | Placenta: Direct evidence of altered IGF/IGFBP signaling in FGR. IGF-Iea and IGF-Ieb show isoform- and compartment-specific changes at the protein level, with reduced IGF-Iea in extravillous trophoblasts but increased IGF-Iea/Ieb immunoreactivity in selected placental vascular and trophoblast compartments, despite largely unchanged mRNA expression. Maternal blood: Increased IGFBP-1/2 and reduced IGF activity have been reported. Cord blood: Reduced IGF-1 is associated with lower birth weight and more severe FGR. | [93,99,100] |
| sFlt-1 | Soluble decoy receptor that binds VEGF and PlGF and regulates their bioavailability. | Increased maternal circulating sFlt-1 and elevated sFlt-1/PlGF ratio are associated with FGR, particularly placental FGR. | Reduces VEGF/PlGF bioavailability, contributing to endothelial dysfunction and impaired uteroplacental perfusion. | Placenta: Increased placental production is implicated in angiogenic imbalance. Maternal blood: Strong evidence; sFlt-1/PlGF ratio is consistently higher in FGR than AGA. Cord blood: Not routinely used or sufficiently validated as an FGR biomarker. | [12,119] |
| p53pathway | Regulates cell-cycle arrest, DNA repair, apoptosis and cellular responses to hypoxia and stress. | Increased p53 expression is associated with increased trophoblast apoptosis in FGR placentas. | Excessive apoptosis, impaired trophoblast survival and reduced placental cellular homeostasis. | Placenta: Direct human evidence of increased p53 in FGR trophoblasts. Maternal blood: Insufficient evidence for routine assessment in FGR. Cord blood: Insufficient evidence for p53 as a validated FGR biomarker. | [122] |
|
PTEN/ PI3K–AKT Axis |
Lipid phosphatase and negative regulator of PI3K/AKT signaling; modulates trophoblast proliferation, migration, invasion, survival, differentiation and placental vascular remodeling. | Dysregulation of the PTEN/PI3K/AKT axis may occur in FGR; reduced PI3K/AKT phosphorylation is reported in human FGR placentas. | Altered PTEN-mediated inhibition of PI3K/AKT may impair trophoblast proliferation, migration, invasion and survival and may contribute to abnormal vascular remodeling and placental insufficiency. | Placenta: Altered PTEN-related signaling is supported, but consistent PTEN overexpression is not established. Maternal blood: PTEN is not an established circulating FGR biomarker. Cord blood: No validated clinical biomarker evidence. | [126,128,129] |
|
ARID1A/ SWI–SNF |
Core regulatory subunit of the SWI/SNF chromatin-remodeling complex that regulates chromatin accessibility and transcriptional programs involved in trophoblast differentiation, proliferation, survival, invasion and cellular stress responses. | Altered ARID1A expression has been reported in placentas with FGR, including increased nuclear expression in syncytiotrophoblasts in FGR and reduced expression in stem-villus veins in late FGR. | Altered ARID1A activity may disturb trophoblast differentiation, proliferation and invasion and may influence placental responses to chronic insufficiency; its specific causal contribution to FGR remains uncertain. | Placenta: Human evidence of altered ARID1A expression in IUGR/FGR placental compartments. Maternal blood: No established ARID1A FGR biomarker. Cord blood: No established clinical evidence. Mechanistic evidence remains limited. | [143] |
| Epigenetic Marks (DNA Methylation, Histone Marks) | Form the functional interface between maternal stress/environment and stable gene expression. | Aberrant global DNA methylation; discrete changes in promoter H3K27ac; downregulations in overall chromatin accessibility. | Drives the long-term transcriptional silencing of crucial angiogenic, structural, and metabolic transport networks. | Placenta: Multi-omics validation confirms widespread epigenomic reprogramming in selective FGR. Maternal/Cord Blood: Cell-free DNA signatures are under investigation. | [139,157] |
| Non-Coding RNAs (miRNAs, lncRNAs) | Provide post-transcriptional fine-tuning and network-wide coordination of target transcripts. | Altered sorting of specific miRNAs (miR-424, miR-15b, miR-146a) and suppression of protective lncRNAs (H19, MALAT1). | Induces simultaneous translational repression of networks coordinating capillary growth, inflammation control, and nutrient transfer. | Placenta: Profiling confirms tissue-specific miRNA–mRNA network disruption. Maternal/Cord Blood: Circulating non-coding RNA signatures show promising early predictive value. | [52,147,150] |
| Nutrient Transporters (SNAT2, LAT1, GLUT Isoforms) | Execute the physical uptake and maternal–fetal transfer of essential amino acids and glucose. | Blunted activity and disrupted membrane trafficking of SNAT2 (System A) and LAT1 (System L); altered expression of GLUT1, 3, and 4. | Directly cuts off the delivery of essential substrates required for fetal structural development, causing metabolic starvation. | Placenta: Confirmed reduction in transporter function, particularly in pregnancies with severely compromised Doppler indices. Maternal/Cord Blood: Unusable as circulating markers. | [153,156,157] |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.