
Submitted:
04 October 2026
Posted:
07 October 2026
You are already at the latest version
Abstract
The DiAL Health Pilot Trial is a well-designed study that measures body mass, fat mass, fat-free mass, and food intake using state-of-the-art methods. Yet its analysis converts these mass measurements into energy equivalents and uses energy as the primary variable. This commentary identifies three loci of energy derivation in the protocol: the weight-loss nomograms, the CR adherence quantification (Equation 1), and the calorie prescription itself. A concrete numerical example shows that energy-based and mass-based analyses can produce divergent results for the same participant. The energy balance equation is mathematically underdetermined with respect to growth composition: one equation, two unknowns. The mass measurements are not. The TRE arm of the trial is not affected by the same issue, because its adherence metric is time-based rather than energy-based. This makes the CR analysis an isolated case rather than a general problem with the trial. A mass-balance analysis would preserve the information that the energy conversion discards, and would produce adherence metrics directly interpretable in the units actually measured. The argument is not that the DiAL Health trial is flawed. It is that the analytical framework it inherited contains a detour that is no longer necessary given the measurements the trial already performs.
Keywords:
mass balance model
; energy balance
; calorie restriction
; adherence
; body composition
; clinical trial methodology
1. The DiAL Health Trial as a Case Study
The Dietary Approaches to Longevity and Health (DiAL Health) Pilot Trial is a 24-week, 5-arm, randomized controlled trial comparing traditional and adaptive approaches to calorie restriction (CR) and time-restricted eating (TRE) in young, healthy adults [1]. The trial is well designed. It uses doubly labeled water to measure energy expenditure under weight-stable conditions, dual-energy X-ray absorptiometry to measure body composition, the Remote Food Photography Method to measure food intake, continuous glucose monitoring to infer meal timing, and internet-connected smart scales to track body weight. These are the best available methods in the field.
The trial also measures mass directly. Body weight is measured in kilograms. Fat mass and fat-free mass are measured in kilograms. Food intake is estimated in grams of macronutrients. These are mass measurements. They are not energy measurements, and they do not require conversion to energy to be interpreted.
Yet the analysis converts them. In three specific places, the protocol takes a quantity that was measured as mass and transforms it into energy before using it as an analytical variable. This commentary identifies those three loci, explains why the conversion is unnecessary, and shows with a concrete example that the two analytical approaches can produce different results for the same participant.
The argument is not that the DiAL Health trial is flawed. It is that the analytical framework it inherited contains a detour that is no longer necessary given the measurements the trial already performs.
2. Three Loci of Energy Derivation
2.1. The Weight-Loss Nomograms
The CR arms of DiAL Health monitor adherence using personalized weight-loss nomograms generated from a validated mathematical model of energy balance [1]. The nomogram predicts a weight-loss trajectory from a calorie prescription, and participants whose measured weight falls outside a predefined adherence zone are flagged as non-adherent.
The model is elegant. But note what it does: it takes a calorie prescription (energy), predicts a weight trajectory (mass), and then compares the prediction with a measured weight (mass). Mass is the input, mass is the output, and energy is the intervening variable. The mass was already available. The energy conversion added a layer of computation without adding information.
2.2. The CR Adherence Quantification (Equation 1).
The protocol quantifies CR adherence as:

Energy intake during the intervention is estimated from an end-of-study measure of energy expenditure adjusted for changes in body composition. Fat mass and fat-free mass changes are converted to energy equivalents using coefficients of 9.3 kcal/g and 1.1 kcal/g, respectively [1].
This is the most consequential locus. The analytical chain is:
- Measure fat mass and fat-free mass in grams (DXA).
- Convert to energy using coefficients (9.3 and 1.1 kcal/g).
- Combine with measured energy expenditure (doubly labeled water).
- Estimate energy intake.
- Compute %CR.
The chain begins with mass, converts to energy, and ends with a percentage that is supposed to describe adherence to a calorie target. The mass measurements are the most direct and most reliable data in the chain. The energy conversions are the least direct.
2.3. The Calorie Prescription Itself
CR participants in DiAL Health receive a calorie prescription equal to 75% of their baseline energy requirements [1]. They are not given a protein target in grams, a fat target in grams, or a carbohydrate target in grams. They are given a single number in kilocalories.
This is the framing choice that shapes everything downstream. If the prescription were in grams of each macronutrient, the adherence metric could be computed directly in grams. Because the prescription is in calories, the adherence metric must be computed in calories, which requires the energy conversions described above.
The calorie prescription is not wrong. But it is the reason the energy detour exists. It is the analytical fork that determines whether the rest of the analysis is conducted in mass or in energy.
3. A Concrete Numerical Example
The claim that the two analyses can produce divergent results is not abstract. Consider two participants in the CR arm, both following the same 25% calorie restriction prescription.
Participant A loses 2.0 kg of fat mass and 0.0 kg of fat-free mass over 12 weeks. The change is entirely adipose.
Participant B loses 1.5 kg of fat mass and 0.5 kg of fat-free mass over the same 12 weeks. The change includes a loss of lean tissue.
Both participants lose 2.0 kg of total body weight. By the calorie-based adherence metric (Equation 1), which uses the composite energy density of the lost tissue, the two are approximately equivalent. The reason is that the energy conversion uses weighted coefficients that smooth over compositional differences: 2.0 kg of fat mass yields about 18,600 kcal, while 1.5 kg of fat mass plus 0.5 kg of fat-free mass yields about 14,500 kcal. Depending on how the coefficients are applied, the difference may be modest, and the calorie-based metric may not flag either participant as non-adherent.
But the two participants are not equivalent. Participant B has lost lean mass – the tissue the trial is designed to protect. The clinical significance is direct: lean mass loss is associated with impaired functional capacity, reduced resting energy expenditure, and, in older adults, increased mortality risk. Participant A has not experienced this loss. Participant B has.
The mass-balance analysis sees the difference immediately, because it reports fat mass and fat-free mass separately. The energy-balance analysis does not, because it collapses them into a single scalar. The composite energy density used in Equation 1 is not a neutral summary. It is an averaging operation that discards the compositional information the trial was designed to collect.
This is not a hypothetical scenario. Compositional heterogeneity during calorie restriction is well documented: some participants lose predominantly fat mass, others lose a substantial proportion of fat-free mass. The trial measures this heterogeneity directly. The analysis discards it.
4. What Is Actually Measured
It is worth listing what DiAL Health actually measures, because the list reveals how much of the analytical work is already done before the energy conversion begins.
Body weight is measured in kilograms by clinic staff and by internet-connected smart scales. Fat mass is measured in kilograms by DXA. Fat-free mass is measured in kilograms by DXA. Food intake is estimated in grams of protein, fat, and carbohydrate by the Remote Food Photography Method. Meal timing is measured in clock time by CGM and by participant self-report.
Every one of these measurements is either a mass measurement or a temporal measurement. None of them is an energy measurement. Energy intake is not measured. Energy expenditure is measured (by doubly labeled water), but it is measured as a rate of isotope elimination, which is itself a mass measurement converted to energy through a calibration equation.
The trial therefore possesses, in its raw data, a complete mass-balance description of each participant. It knows how many grams of protein, fat, and carbohydrate were consumed. It knows how many grams of fat mass and fat-free mass were gained or lost. It knows the body weight at each time point. It has everything required for a mass-balance analysis.
What it does not have is a mass-balance analysis. It has an energy-balance analysis that uses the mass measurements as inputs to an energy conversion.
5. Why the Energy Detour Matters
The energy detour is not merely inelegant. It has three specific costs.
5.1. It Discards Information
The mass-balance description specifies the change in fat mass and the change in fat-free mass separately. The energy-balance description collapses them into a single scalar: total stored energy. Once the collapse has occurred, the information about composition is no longer present in the analytical output. It can only be recovered if the original mass measurements are retained – which, in this trial, they are. But the reported metric, %CR, does not carry the compositional information forward.
5.2. It Introduces Assumptions
The energy conversion requires coefficients: 9.3 kcal/g for fat mass, 1.1 kcal/g for fat-free mass. These coefficients are not measured in the trial. They are assumed. The values vary with tissue hydration, with the proportion of extracellular to intracellular water, and with the composition of the fat-free mass itself. A change in the assumed coefficient propagates directly into the %CR estimate.
5.3. It Creates a Circular Inference
The energy-balance equation is underdetermined with respect to composition:
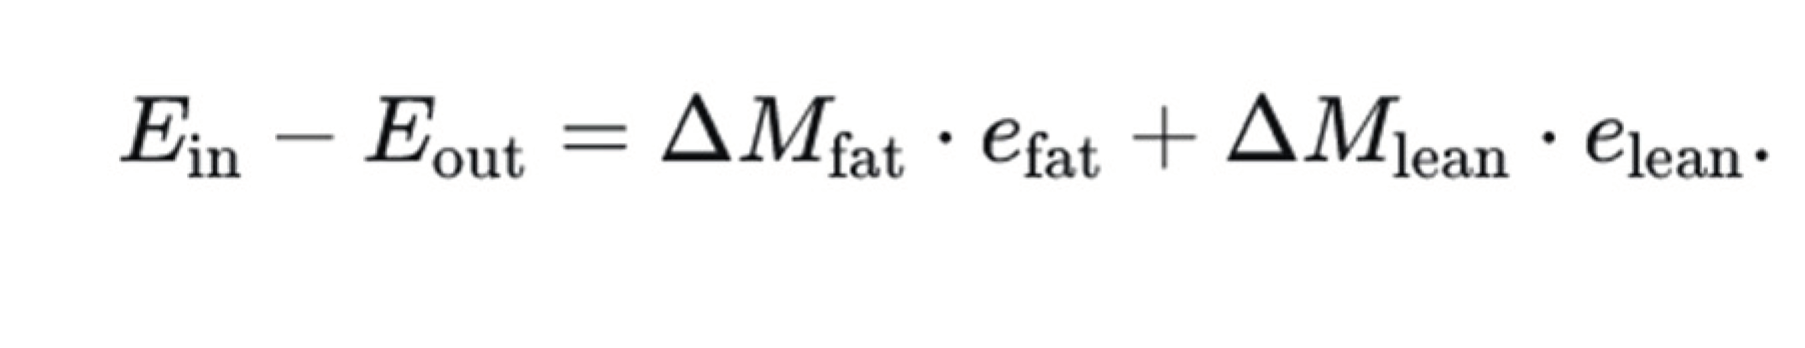
This is one equation with two unknowns. The energy balance specifies the total stored energy. It does not specify how that energy is distributed between fat and lean mass. There are infinitely many combinations of ∆Mfat and ∆Mlean that satisfy the same energy balance. No amount of additional energy-balance data can resolve the ambiguity, because the framework itself does not contain the information required to resolve it.
This is the structural problem. The energy-balance framework cannot specify growth composition. The mass-balance framework can, because composition is its primary variable. The DiAL Health trial measures composition directly. The analysis then discards it.
6. The TRE Arm Is Not Affected
It is important to note that the TRE arm of DiAL Health does not suffer from the same problem. The TRE adherence metric (Equation 2) is based on the duration of the eating window, not on energy intake. It measures the time from the first eating event to the last, and computes adherence as the deviation from a prescribed 8-hour window.
This is a temporal metric, not an energy metric. It does not require energy conversion. It is computed directly from the measured eating events, which are timestamped. It is, in effect, already a mass-independent analysis.
This precision matters for two reasons. First, it shows that the CR analysis is an isolated case, not a general problem with the trial. The TRE arm demonstrates that DiAL Health is capable of designing metrics that do not require energy conversion. Second, it clarifies what the CR arm could become: a metric that preserves the mass information that was actually measured, in the same way the TRE arm preserves the timing information that was actually measured.
The comparison strengthens the argument. The TRE arm shows that non-energy-based adherence metrics are already feasible within the same trial. The CR arm could follow the same principle.
7. What a Mass-Balance Analysis Would Look Like
Primary variables. Grams of protein, fat, and carbohydrate consumed per day. Grams of fat mass and fat-free mass gained or lost over the intervention. Body weight in kilograms at each time point.
Derived variables. Protein-energy ratio (PER), computed as grams of protein per 100 kcal of total intake. Macronutrient distribution, computed as percentage of total mass or percentage of total energy, depending on the question.
Adherence metric. Percentage of prescribed protein mass consumed, percentage of prescribed fat mass consumed, percentage of prescribed carbohydrate mass consumed. These are computed directly from the food intake measurements, without an energy conversion.
Comparison metric. Change in fat mass and change in fat-free mass, reported separately. These are computed directly from the DXA measurements, without an energy conversion.
The mass-balance analysis would produce results that are directly interpretable in the units that were measured. It would preserve the compositional information that the energy conversion discards. It would not require the assumed energy coefficients. And it would be robust to the structural underdetermination of the energy-balance equation, because mass balance does not suffer from that underdetermination.
The two analyses are not mutually exclusive. The energy-balance analysis can be retained as a secondary analysis. But the mass-balance analysis should be primary, because it uses the data in their native units and preserves the information that the trial was designed to collect.
8. What Future Trials Should Do
The critique of DiAL Health generalizes. Future CR trials that measure body composition directly should consider three protocol-level changes.
Prescribe in grams. Instead of prescribing a single calorie target, prescribe grams of protein, fat, and carbohydrate. This is not a rejection of calorie counting; it is a refinement. The calorie target can be retained as a derived quantity, but the primary target is in mass. This change alone eliminates the need for the energy conversion in the adherence metric.
Report in both domains. Report results in mass and in energy, side by side. If the two domains produce the same conclusions, the energy analysis is validated. If they produce different conclusions, the mass analysis should be treated as primary, because it uses the data in their native units.
Report composition separately. Never report a change in body weight without reporting the change in fat mass and fat-free mass separately. Weight is the sum of compositionally distinct compartments, and the sum obscures what matters. The DXA measurements already provide the composition data. The analytical output should carry it forward.
None of these recommendations requires new measurements. They require a shift in which variables are treated as primary. The measurements that support mass-balance analysis are already being collected. The framework is the only missing piece.
9. Predictions
If the mass-balance analysis is performed alongside the energy-balance analysis, four predictions follow.
Prediction 1: Mass-balance adherence will diverge from energy-balance adherence in some participants. Participants whose fat mass and fat-free mass change in proportions different from the assumed coefficients will show discrepancies between the two adherence metrics. This is directly testable with the trial data.
Prediction 2: The divergence will correlate with protein intake. Participants with higher protein intake will show greater fat-free mass retention, which will make the energy-balance adherence metric less accurate. This is testable with the food intake data and the DXA data together.
Prediction 3: The nomogram’s adherence zone will be less accurate for participants with atypical body composition. Participants with high baseline fat-free mass or low baseline fat mass will deviate from the nomogram’s predictions more than participants with typical body composition. This is testable with the baseline DXA data and the weekly weight data.
Prediction 4: The mass-balance analysis will identify adherence patterns that the energy-balance analysis misses. Participants who adhere to the protein prescription but not the fat or carbohydrate prescription will be invisible to a calorie-based adherence metric but visible to a mass-based one. This is testable with the food intake data.
10. Conclusion
The DiAL Health Pilot Trial measures mass directly. Body weight, fat mass, fat-free mass, and macronutrient intake are all measured as mass. The measurements are state-of-the-art. The data are already sufficient for a complete mass-balance analysis.
The analysis converts these measurements to energy and uses energy as the primary variable. This conversion is not required by the data. It is a consequence of the energy-balance framework in which the trial is embedded.
The conversion has three costs. It discards the compositional information that the mass measurements contain. It introduces assumed coefficients that propagate into the adherence metric. And it creates a circular inference in which mass is converted to energy and then back to mass, without adding information at any step. A concrete numerical example shows that the same total weight loss can mask compositionally distinct trajectories, and that the energy-based metric cannot distinguish between them.
The TRE arm of the trial demonstrates that non-energy-based adherence metrics are already feasible within the same protocol. The CR arm could follow the same principle.
A mass-balance analysis would preserve the information that the trial was designed to collect. It would produce adherence metrics directly interpretable in the units that were measured. It would not require the assumed energy coefficients. And it would be robust to the structural underdetermination of the energy-balance equation.
The recommendation is not to discard the energy-balance analysis. It is to elevate the mass-balance analysis to primary status, because it uses the data in their native units and preserves the information that the trial was designed to collect. The measurement is already mass. The analysis should be too.
Note on Tone
This commentary is not a critique of the DiAL Health investigators. The trial is well designed, the measurements are state-of-the-art, and the analysis follows the conventions of the field. The critique is of the framework itself: the energy-balance convention that converts mass measurements into energy before using them as analytical variables. The DiAL Health trial provides an unusually clear case study because it measures mass so directly. That clarity makes the energy detour visible in a way that less rigorous trials do not. The recommendations above are refinements, not rejections.
Author Contributions
This is a single-authored paper.
Ethics Approval and Consent to Participate: Not applicable.
Consent for Publication: Not applicable.
Availability of Data: All data generated or analyzed during this study are contained in the sources cited.
Funding
This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Acknowledgments
I thank the DiAL Health investigators for the clarity of their protocol, which made this analysis possible.
Conflicts of Interest
The author declares no conflict of interest.
References
- Kennedy, S.F.; Cabre, H.E.; Diktas, H.E.; et al. Rationale and Design of Traditional and Adaptive Calorie Restriction and Time-Restricted Eating Interventions Used in the Dietary Approaches to Longevity and Health (DiAL Health) Pilot Trial. Curr. Dev. Nutr. 2026, 10(9), 109461. [Google Scholar] [CrossRef] [PubMed] [PubMed Central]
- Manninen, A.H. Mass Balance over Energy Balance: Why Direct Mass Accounting Offers a More Precise and Mechanistically Faithful Framework for Human Body Weight Regulation. Preprints 2026, 2026040690. [Google Scholar] [CrossRef]
- Manninen, A.H. Implementing the Mass Balance Model (MBM) in Human Nutrition and Obesity Research: Protocols, Analytical Frameworks, and Translational Applications. Preprints 2026, 2026041641. [Google Scholar] [CrossRef]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.