

Submitted:
04 October 2026
Posted:
07 October 2026
You are already at the latest version
Abstract
Type 1 diabetes mellitus (T1D) is an autoimmune disease driven by a complex interplay between genetic susceptibility, environmental factors, and dysregulated immune re-sponses, ultimately leading to the progressive destruction of insulin-producing pancre-atic β-cells. Despite substantial advances in glucose monitoring and insulin delivery technologies, current treatment strategies cannot fully reproduce the physiological regu-lation of insulin secretion and do not directly target the underlying autoimmune process. Consequently, increasing attention has been directed toward immunomodulatory ap-proaches aimed at preserving residual β-cell function and modifying disease progres-sion. Mesenchymal stromal cells (MSCs) have emerged as a promising cell-based thera-peutic approach owing to their broad immunomodulatory, anti-inflammatory, and paracrine properties. Importantly, unlike therapies directed predominantly at individual immune targets or pathways, MSCs can simultaneously modulate multiple intercon-nected mechanisms involved in T1D immunopathogenesis, affecting both innate and adaptive immune responses, inflammatory signaling, antigen presentation, and immune tolerance. This broad and multifaceted mode of action provides a strong rationale for in-vestigating MSCs as a therapeutic strategy capable of addressing the complex and highly interconnected nature of T1D autoimmunity. This review examines the major mecha-nisms underlying T1D immunopathogenesis and the multifaceted immunomodulatory effects of MSCs, followed by a critical evaluation of the available preclinical and clinical evidence on MSC-based therapy. The potential of MSCs to preserve β-cell function, mod-ulate immune responses, and improve metabolic outcomes is considered, together with current limitations and challenges for clinical translation.
Keywords:
type 1 diabetes mellitus
; mesenchymal stromal cells
; autoimmunity
; cell-based therapy
; immunomodulation
1. Introduction
Type 1 diabetes mellitus remains a leading global medical and societal challenge, characterized by the early-age disease onset, lifelong dependence on exogenous insulin therapy, rigorous follow-up requirements, and substantial healthcare expenditure [1,2]. Insulin replacement therapy, currently the only established means of sustaining life in patients with type 1 diabetes (T1D), is not flawless [3]. Despite considerable advances in continuous glucose monitoring systems and insulin pump technology, exogenous insulin cannot replicate the fine, dynamic regulation of glucose metabolism ensured by healthy β-cells [4]. As a result, patients experience persistent blood glucose fluctuations that substantially increase the risk of severe hypoglycemia or hyperglycemia—which not only impair quality of life but also drive higher rates of cardiovascular complications and overall mortality [5].
The fundamental limitation of T1D therapy is that insulin administration is purely substitutive: it compensates for hormone deficiency but remains entirely inert with respect to the immunopathogenesis of the disease. Exogenous insulin does not modulate the activity of autoreactive T- and B-lymphocytes, nor does it restore disrupted immune tolerance. Consequently, autoimmune aggression continues to progress unabated, gradually eliminating residual pancreatic β-cells even under optimally adjusted insulin regimens [3,6]. Thus, even the most advanced insulin delivery strategies—including multiple daily injections, insulin pumps, and continuous glucose monitoring—designed to mimic natural hormone secretion as closely as possible, cannot fully prevent the development of long-term diabetic complications. The risk of progressive damage to blood vessels, peripheral nerves, and kidneys (diabetic neuropathy, nephropathy, and retinopathy) remains substantially elevated over the long term, because replacement therapy does not address the underlying metabolic and inflammatory processes that drive these injuries [7]. Given these limitations, the search for novel T1D therapies aimed at modulating immune responses and preserving endogenous islet function represents a critically important frontier in contemporary endocrinology and regenerative medicine.
Over the past few decades, cell-based technologies and targeted immunotherapies have advanced rapidly, shifting the focus of clinical research from symptomatic metabolic correction toward direct intervention in the immunopathogenesis of T1D. Fundamentally, these strategies are aimed at the restoration of immune tolerance to islet autoantigens, thereby addressing the root cause of the disease rather than its clinical consequences [8].
One of the earliest approaches involved monoclonal antibodies targeting the CD3 receptor (otelixizumab, teplizumab). Anti-CD3 therapy modulates T-cell activity, pushing autoreactive clones into a state of functional unresponsiveness while promoting an expansion of regulatory T-cells that suppress autoimmune inflammation. Large-scale clinical trials have demonstrated that teplizumab can delay the progression of T1D by 2–3 years in individuals at high genetic risk [9]. Selective depletion of B-lymphocytes with anti-CD20 antibodies (rituximab) is designed to interrupt their antigen-presenting function—through which B-cells activate autoreactive T-helpers—and to reduce the production of pathogenic autoantibodies that mediate antibody-dependent cell-mediated cytotoxicity against β-cells. In a randomized phase II trial, rituximab showed statistically significant but transient preservation of C-peptide secretion. However, by 12 months, the beneficial effect gradually waned, as the therapy also depleted the pool of regulatory B-cells, which are critically important for maintaining immune tolerance [10,11].
An alternative strategy—low-dose interleukin-2 (IL-2) administration—selectively stimulates the proliferation and functional activity of CD4⁺CD25⁺FoxP3⁺ regulatory T-cells (Tregs) without activating effector lymphocytes. Pilot and phase-I studies have confirmed the safety of low-dose IL-2 and its capacity to expand the Treg pool in vivo; however, its clinical relevance in terms of sustained glycemic control and reduced insulin requirements remains modest and appears to require extended treatment courses [12,13].
Personalized cell-based approaches include treatment with tolerogenic dendritic cells (tolDCs) and adoptive therapy with autologous Tregs that are expanded ex vivo to reach therapeutic concentrations. tolDCs, generated ex vivo in the presence of immunosuppressive cytokines, present islet antigens in a tolerogenic context that induces immune tolerance, thereby triggering antigen-specific suppression without global immunosuppression. Early phase I/II clinical trials have confirmed the safety and immunological activity of tolDCs, but have also revealed considerable variability in response depending on the culture protocol and antigen loading [14,15]. Adoptive Treg therapy aims to directly replenish the suppressor cell pool. Despite encouraging phase I data on safety and cell migration to lymphoid organs, challenges remain in scaling up production, preserving a stable phenotype after infusion, and the need for repeated administrations—all of which represent substantial technological hurdles [16,17].
Despite theoretical rationale, all of the above approaches face fundamental limitations. Targeted antibody-mediated therapies (anti-CD3, anti-CD20) are often associated with the risk of unintended systemic immunosuppression, infectious complications, infusion-related reactions (fever, chills, hypotension), and lymphopenia; they are also characterized by transient efficacy, necessitating repeat courses and driving up treatment costs [9,10]. Personalized cell-based products derived from tolDCs and Tregs present considerable challenges in terms of standardizing GMP-grade manufacturing, a narrow therapeutic window, and marked dependence on individual patient immunologic profiles [18,19]. Furthermore, most of these interventions target a single component of the immune cascade, whereas the autoimmune process in T1D constitutes a complex network characterized by high plasticity, cross-reactivity, and compensatory mechanisms—all of which diminish the efficacy of mono-targeted approaches [20].
Mesenchymal stromal cell (MSC)-based therapies are largely free of many of the limitations inherent to the therapeutic approaches described above. Their effects on the recipient's immune system are pleiotropic [21]. Unlike narrowly targeted agents, mesenchymal stromal cells (MSCs) possess an intrinsic capacity to modulate a broad range of immune processes: they induce functional anergy in autoreactive T-lymphocytes and promote expansion of regulatory T-cells (Tregs) [22]; suppress B-cell proliferation and the production of pathogenic autoantibodies [23]; block dendritic cell maturation; and shift the macrophage phenotype from a pro-inflammatory (M1) to an anti-inflammatory (M2) profile [24], while simultaneously normalizing the systemic cytokine milieu. A key feature is that this immunomodulation occurs without inducing systemic immunosuppression or cytotoxicity, thereby preserving the host's ability to combat infections and maintain immune surveillance [25]. The clinical safety and therapeutic efficacy of various MSC types (bone marrow-derived, adipose-derived, umbilical cord-derived) have already been substantiated in randomized trials for a range of severe autoimmune and immune-mediated conditions. Specifically, allogeneic MSCs have demonstrated marked efficacy in treating acute graft-versus-host disease [26], have been shown to induce remission in refractory systemic lupus erythematosus [27], and to slow neuroinflammation in progressive forms of multiple sclerosis [28].
Given that the pathogenesis of T1D is a complex immunopathological process involving diverse effector cell populations, cross-reactivity, and compensatory mechanisms, the ability of MSCs to simultaneously target multiple steps of the immune cascade makes them a promising candidate for disease-modifying therapy [20]. The unique combination of their broad immunomodulatory profile, robust paracrine activity, and a favorable safety record provides a strong scientific rationale for active exploration of MSCs in the context of inducing durable antigen-specific tolerance and preserving long-term β-cell function in T1D [29,30].
The aim of this review is to analyze and synthesize the available evidence on the therapeutic potential of MSCs in T1D. Since autoimmune β-cell destruction lies at the core of the disease, particular emphasis is placed on the regenerative and immunomodulatory properties of MSCs that allow them to target key nodes of T1D immunopathogenesis, as well as on findings from preclinical and clinical studies that either support or limit the efficacy of this approach. A separate aspect of the analysis concerns the impact of the hyperglycemic diabetic microenvironment on the functional activity of transplanted MSCs, which determines the real-world effectiveness of cell-based therapy under disease conditions. Finally, the review broadens the perspective beyond islet preservation by assessing the ability of MSCs to modulate systemic autoimmune inflammation underlying long-term complications—diabetic neuropathy, nephropathy, and retinopathy—which remain clinically relevant even after complete loss of pancreatic endocrine function. Collectively, the work aims to provide a comprehensive picture of where MSC therapy stands in the current treatment paradigm for T1D: from pathophysiological rationale to unresolved challenges and prospects for clinical translation.
2. Epidemiology and Global Burden of T1D
Epidemiological data point to marked geographic heterogeneity and a steady global rise in the incidence of T1D [31]. Current estimates from a systematic review and meta-analysis indicate that T1D accounts for roughly 9.5% of all diabetes cases worldwide, with annual incidence ranging from 0.5 to 40 new cases per 100,000 persons depending on the region [32]. Historically, the highest incidence rates have been reported in Finland, Sardinia (Italy), and Sweden, where they exceed 30–40 cases per 100,000 children per year, whereas in East Asian countries (Japan, China) rates remain below 5 per 100,000 [4]. Between 1989 and 2003, the average annual increase in incidence among European children aged 0–14 years was 3.9%, with the most pronounced rise occurring in the 0–4 year age group [33]. A subsequent systematic review confirmed a similar upward trend in young adults: in Scandinavia, the United Kingdom, and Canada, T1D incidence in individuals 15–40 years of age rose by 2–5% annually, indicating that the disease is extending beyond the pediatric age range [34]. Although traditionally viewed as a disorder primarily affecting children and adolescents, the past few decades have witnessed a marked rise in the frequency of adult-onset cases. Consequently, efforts to refine clinical management and advance pathogenesis-oriented therapeutic strategies must remain inclusive of all age groups [35].
Unfortunately, the previously projected rise in T1D incidence has not only materialized but has also taken on new demographic features. According to current global estimates for 2025, approximately 9.5 million people worldwide are living with T1D, of whom 1.85 million are children and adolescents under 20 years of age [36]. Whereas past decades placed major emphasis on the explosive increase in incidence among young children, more recent studies document a sustained global rise in incidence among adolescents as well [37]. Moreover, the paradigm of T1D as an exclusively "juvenile" disease has now been definitively revised: current epidemiological models indicate that 64% of all new T1D cases are diagnosed in individuals aged 20 years and [38]. In developed countries, including the United States, T1D prevalence among adults now exceeds that among children, with approximately 5 cases per 1,000 adults versus 4 cases per 1,000 children and adolescents as of 2019–2022 [39]. Mathematical modeling of current trends suggests that if the observed rates of incidence growth persist, the total number of T1D cases in the population could increase by roughly 65% over the coming decades [40].
The data presented support the hypothesis that environmental, ethnic, and socioeconomic factors exert a substantial influence on the course of the autoimmune process, which is consistent with findings from international studies documenting regional differences in disease incidence [41]. Genetic background currently appears to play a less decisive role in disease development than it did in the past. Epidemiological evidence suggests that environmental triggers are increasingly initiating the autoimmune process in individuals with modest or low hereditary susceptibility, positioning the immune system as a key modifiable target for therapeutic intervention [42,43]. An important positive trend is the increased life expectancy of patients with T1D: the median disease duration from onset to death rose from 15.4 to 19.9 years over the observation period, while the mean age at death reached 52.7 years [44]. Nevertheless, glycemic control targets remain inadequately met, with only 34.7% of T1D patients achieving an HbA1c level below 7.0%—underscoring the pressing need for disease-modifying therapies capable not only of replacing insulin but also of curbing the autoimmune process [45].
3. Immunopathogenesis of T1D and Therapeutic Targets for Cell Based Approaches
3.1. Genetic Susceptibility and Triggering factors
The development of T1D is driven by a complex interplay between genetic predisposition and environmental triggers, which jointly disrupt the mechanisms of immune tolerance. To date, more than 40 genetic loci influencing T1D susceptibility have been identified, with approximately 40–50% of the hereditary risk associated specifically with human leukocyte antigen (HLA) genes, which determine the presentation of autoantigens to the immune system [46]. The highest risk is conferred by the haplotypes DRB103:01-DQA105:01-DQB102:01 and DRB104:05-DQA103:01-DQB103:02, named in serological nomenclature as DR3-DQ2 and DR4-DQ8, respectively. These haplotypes associated with MHC class II molecules with a specific peptide-binding groove structure that presents islet autoantigens (such as insulin, glutamic acid decarboxylase 65 (GAD65), IA-2, and ZnT8) to autoreactive CD4⁺ T lymphocytes [47]. Heterozygosity for DR3/DR4 multiplicatively increases the risk of clinical disease onset, whereas the HLA-DQB1*06:02 allele exerts a pronounced protective effect by promoting robust central tolerance in the thymus [48].
Beyond the HLA region, genome-wide association studies have identified more than 60 non-HLA loci that collectively explain up to 15% of the genetic risk, with polymorphisms in the PTPN22, CTLA4, and IL2RA genes playing a key role [49,50]. The PTPN22 R620W variant alters the activity of the LYP tyrosine phosphatase, leading to a lowered T-cell receptor activation threshold and allowing autoreactive clones to escape negative selection [51]. Certain CTLA4 polymorphisms weaken the inhibitory signal required for the induction of T-lymphocyte anergy and the functional activity of regulatory T cells [52]. Variations in the IL2RA (CD25) gene can disrupt the expression of the interleukin-2 receptor α-chain, critically impairing the survival, proliferation, and suppressive function of Tregs that maintain peripheral tolerance [53].
However, carrying predisposition alleles alone is insufficient for disease manifestation. The initiation of the autoimmune process is triggered by environmental factors acting during early-life immune system development. Viral infections, primarily enteroviruses including Coxsackievirus B, are considered the most likely triggers, initiating pathogenesis through mechanisms of molecular mimicry, immune cell activation at sites of inflammation, and direct viral destruction of β-cells [54,55]. Gut microbiota dysbiosis, characterized by reduced microbial diversity, a deficit of short-chain fatty acid-producing bacteria, and impaired intestinal barrier permeability, leads to systemic pro-inflammatory activation and disrupted differentiation of regulatory lymphocytes [56,57]. Dietary factors also contribute significantly: the early introduction of cow's milk and gluten, along with deficiencies in vitamin D and omega-3 polyunsaturated fatty acids, correlate with an increased risk of developing autoantibodies against pancreatic islet cells. This has been confirmed by large-scale prospective studies tracking children with genetic risk from birth to clinical onset [58,59]. The cumulative effect of these triggers in a genetically predisposed individual disrupts the balance between the effector and regulatory arms of the immune system, creating the conditions for the initiation of irreversible β-cell destruction (Figure 1).
3.2. Impaired Immune Tolerance and Activation of Autoreactive Clones
The development of autoimmune attack in T1D begins with a failure of the mechanisms that ensure immune tolerance to self-tissues. Central tolerance, which develops in the thymus for T cells and in the bone marrow for B cells, involves the negative selection and elimination of cells with high affinity for autoantigens. In T1D, this process is disrupted due to insufficient expression of tissue-specific antigens (primarily insulin) in the thymus, allowing autoreactive clones to escape deletion and exit the primary lymphoid organs [60]. Furthermore, polymorphisms in the PTPN22, CTLA4, and IL2RA genes affect the T-cell receptor activation threshold, weakening the efficiency of negative selection in the thymus and increasing the release of potentially pathogenic autoreactive cells into the peripheral immune system [51]. Mechanisms of peripheral tolerance, designed to control lymphocytes that have escaped central tolerance within secondary lymphoid organs and target tissues, include functional anergy, apoptosis, and suppression by Tregs. In T1D, a quantitative and/or functional deficit of Tregs is observed, along with increased resistance of effector T cells to their suppressive action, which disrupts the balance between immune response activation and inhibition [61]. As a result, lymphocytes specific to islet cell antigens retain their proliferative activity and pathogenic potential in the peripheral compartment.
The key link connecting autoreactive clones that have escaped immune tolerance to the initiation of tissue-specific inflammation is dendritic cells (DCs). These professional antigen-presenting cells capture, process, and present β-cell autoantigens (insulin, GAD65, IA-2, ZnT8) in complex with MHC-II molecules to naive CD4⁺ T lymphocytes [62,63]. In the presence of genetic predisposition and an environmental trigger, DCs acquire a hyperactivated phenotype: they upregulate the expression of costimulatory molecules (CD80, CD86, CD40) and secrete pro-inflammatory cytokines (IL-12, IL-6, IFN-α), which skews T-helper differentiation toward T-helper 1 (Th1) and T-helper 17 (Th17) lineages, thereby promoting effector T-cell cytotoxicity [64]. The presentation of insulin and GAD65 by DCs in the pancreatic lymph nodes plays a decisive role in initiating the clonal expansion of autoreactive T cells. These cells subsequently migrate to the pancreas and form an inflammatory infiltrate in the islets of Langerhans, leading to progressive β-cell destruction [62]. Thus, the disruption of tolerance during lymphocyte selection, followed by the hyperactivation of DCs, creates the immunological foundation for the irreversible autoimmune destruction of pancreatic β-cells.
A key mechanism in the immunopathogenesis of T1D is the breakdown of central tolerance through the formation of neoantigens — modified or hybrid β-cell proteins that are absent from the thymus during T-cell selection. These include hybrid insulin peptides, generated by fusion of insulin fragments with other islet proteins within the processing compartments of antigen-presenting cells [65,66]. Additionally, under conditions of oxidative stress and local inflammation, native autoantigens undergo post-translational modifications, such as oxidation and deamidation, which radically alter their immunogenicity and enable their recognition by effector T-cells [67]. One example is the C19S insulin B-peptide, recognized in the context of HLA-DQ8 by T-cells [68]. Such peptides result from oxidative stress-induced modification of the cysteine thiol group. This process can occur during the disposal of unused secretory granules, which fuse with lysosomes to form crinosomes [69].
Viral burden also induces the expression of cryptic protein fragments and atypical structural variants of proinsulin, which serve as additional targets of the autoimmune attack [70,54]. It is precisely the presentation of these altered antigenic forms by dendritic cells in pancreatic lymph nodes that drives clonal expansion of neoepitope-specific T-cells and establishes a sustained pool of effector cells that migrate to the pancreas to execute inflammatory infiltration [71].
3.3. Effector mechanisms of β-cells destruction.
The direct destruction of insulin-producing cells is driven by the coordinated interaction of the cellular and humoral arms of the immune system, which together mediate the irreversible autoimmune destruction of pancreatic islet β-cells.
The T cell compartment serves as the primary effector arm of the autoimmune cascade. CD8⁺ cytotoxic T lymphocytes directly destroy β cells through two main pathways: the release of perforin and granzymes, which form pores in the cell membrane—with limited damage triggering an apoptotic cascade via granzyme B mediated activation of intracellular caspases, whereas extensive perforation leads to uncontrolled necrosis. In addition, FasL Fas interaction between the lymphocyte and the β cell induces an apoptotic signal through the extrinsic caspase 8 activation pathway [4,72].
CD4⁺ Th1 cells have traditionally been viewed not as direct effectors of destruction but rather as orchestrators of the immune response. By releasing INF-γ, they activate macrophages and enhance antigen presentation on β cells via MHC I. Furthermore, IFN-γ drives ectopic expression of MHC II on β cells, converting them into non professional antigen presenting cells, which in turn may stimulate autoantigen specific CD4⁺ T helpers [73,74]. Collectively, these processes create a sustained proinflammatory milieu that renders the islets highly vulnerable to CD8⁺ mediated destruction [4].
It should be noted, however, that direct cytotoxicity of CD4⁺ T cells via perforin granzyme and Fas/FasL pathways has been demonstrated in other autoimmune conditions, most notably multiple sclerosis, where CD4⁺ cells are capable of directly damaging oligodendrocytes [75,76]. In the context of T1D, however, a direct cytotoxic role for CD4⁺ cells remains unproven, and their contribution to β cell destruction is considered to occur primarily through regulatory and proinflammatory mechanisms.
The immunopathological cascade is further amplified by Th17 cells, which produce IL 17 and thereby stimulate pancreatic epithelial and stromal cells to secrete chemokines (CXCL1, CXCL8) that actively recruit neutrophils to the inflammatory site. Infiltrating neutrophils release reactive oxygen species and proteolytic enzymes, exacerbating oxidative stress and accelerating islet tissue destruction [77].
The B-cell arm in T1D serves primarily regulatory and marker functions [4]. B lymphocytes produce autoantibodies against insulin, GAD65, IA-2, and ZnT8, which serve as highly specific diagnostic markers of the autoimmune process and predictors of the disease progression rate [78]. However, research data clearly indicate that the autoantibodies themselves are not the primary effectors of tissue damage: they do not directly trigger β-cell destruction, but rather reflect the activation of the B-cell compartment. This compartment sustains chronic inflammation through the release of cytokines and participates in the presentation of islet autoantigens to CD4⁺ T helper cells, forming a cycle of mutual B- and T-lymphocyte activation [79].
The culmination of this pathogenic cascade involves activated M1-polarized macrophages that infiltrate the islets of Langerhans and secrete high concentrations of pro-inflammatory cytokines, including IL-1β, TNF-α, and IL-6 [80]. These mediators induce the expression of inducible nitric oxide synthase (iNOS) in β-cells, leading to the accumulation of toxic nitric oxide and the disruption of mitochondrial function [81]. IL-1β and TNF-α directly activate caspases and suppress the expression of genes responsible for insulin secretion, triggering apoptosis even in cells that have not yet been subjected to direct T-lymphocyte attack. IL-6, in turn, sustains chronic inflammation, stimulates the proliferation of effector T cells, and suppresses the generation of regulatory cell populations, thereby closing the loop of uncontrolled destruction [81,82].
The pathological process in the pancreas occurs in stages: from initial perivascular infiltration by immune cells to the subsequent penetration of lymphocytes and macrophages into the islet parenchyma, culminating in irreversible destruction and the complete loss of endocrine function [80]. Due to the gradual nature of this process, the concept of preserved β-cell function defines early therapeutic intervention as a critical "window of opportunity": maintaining even minimal endogenous insulin secretion is associated with better glycemic control, a reduced risk of severe hypoglycemia, and a delay in the development of vascular complications [83,84]. To evaluate the dynamics of autoimmune aggression, validated biomarkers are used: islet autoantibody titers (GAD65, IA-2, ZnT8) reflect the activity of the humoral arm; C-peptide levels serve as the gold standard for measuring preserved β-cell mass; and the immunological profile (Treg/Th17 ratio, cytokine status) allows for the monitoring of responses to immunomodulatory therapy [78,85]. Understanding these stages and biomarkers forms the pathophysiological basis for the use of mesenchymal stromal cells, whose mechanisms of action in preclinical and clinical studies are directed precisely at interrupting this cascade during the initial stages of β-cell destruction and ensuring the long-term preservation of pancreatic islet function.
4. Regenerative and Immunomodulatory Properties of MSCs
MSCs were first isolated from the bone marrow [86], and consequently, bone marrow-derived MSCs are currently the most thoroughly characterized, making them a sort of "gold standard" for describing the properties and functions of this cell type. MSCs are defined as cells meeting the following criteria: the ability to adhere to plastic after isolation, the capacity for multilineage differentiation into mesodermal lineage cells (adipocytes, chondrocytes, osteocytes) in vitro, surface expression of CD90, CD73, and CD105 markers, and the absence of hematopoietic marker expression (CD11b, CD14, CD34, CD45, HLA-DR) [87]. Cells with these characteristics can be isolated from virtually all mammalian organs and tissues, including adipose tissue, lungs, liver, extraembryonic tissues (umbilical cord, placenta, amniotic fluid), synovial fluid, dental pulp of deciduous teeth, and others.
In addition to the previously described characteristics, MSCs possess a range of other properties that make them a promising therapeutic tool for treating various diseases. In particular, MSCs exhibit significant regenerative potential. By migrating to the site of injury, they can initiate processes aimed at tissue repair, primarily by suppressing the death of resident cells, stimulating their proliferation and the differentiation of resident stem and progenitor cells, inducing angiogenesis, and exerting a protective effect on the damaged tissue cells [88,89]. The most therapeutically important feature of MSCs is their pronounced immunomodulatory capacity [90,91]. Numerous studies have demonstrated their ability to suppress the proliferation and activation of T lymphocytes and stimulate the expansion of Tregs [92]. MSCs suppress the proliferation of natural killer (NK) cells, induce their apoptosis, modulate cytokine secretion (IFN-γ and TNF-α), enhance degranulation, and inhibit their cytotoxic function [93]. MSCs stimulate the metabolic reprogramming of macrophages, resulting in a phenotypic shift from the pro-inflammatory M1 state to the anti-inflammatory/pro-regenerative M2 phenotype [94,95]. They also exert a wide range of other effects on immune cells, ultimately leading to the fine-tuning of immune-mediated processes including T1D (Table 1).
It is now well established that all these MSC effects, whether regenerative or immunomodulatory, are primarily mediated through paracrine mechanisms, i.e., via the MSC secretome. The MSC secretome comprises a diverse array of cytokines, chemokines, growth factors, extracellular matrix proteins, and extracellular vesicles (exosomes, microvesicles, apoptotic bodies) [96]. The therapeutic efficacy of the MSC secretome, including conditioned media and isolated extracellular vesicles, has been shown to be comparable to that of the parent cells [97,98]. Depending on culture conditions or specific preconditioning, the MSC secretome can be directed to achieve more pronounced therapeutic effects [99,100]. Methods for MSC preconditioning have been developed to enhance the secretion of extracellular vesicles with specific compositions and properties [101].
Although MSCs isolated from different tissues generally share common properties, tissue-specific characteristics related to their origin cannot be excluded. Indeed, depending on their tissue source, MSCs may differ in surface marker expression levels, proliferation rates, and the ability to differentiate into mesodermal lineage cells. For example, bone marrow-derived MSCs (BM-MSCs) efficiently differentiate in all three directions: osteogenic, adipogenic, and chondrogenic. In contrast, umbilical cord MSCs have very low osteogenic potential, while liver-derived MSCs differentiate efficiently in the osteogenic and chondrogenic directions but show almost no adipogenic differentiation. The spectrum of secreted factors and the immunomodulatory properties can also vary significantly among different MSC types [102,103,104,105]. Using RNA sequencing methods, including bulk RNA-seq, scRNA-seq, and snRNA-seq, it has been shown that MSCs isolated from different tissues exhibit specific gene expression profiles with a substantial set of differentially expressed genes. This is likely related not only to their lineage commitment based on tissue origin but also defines their narrower functional specialization, which can significantly influence their therapeutic potential in various pathologies [106,107,108].
As immunomodulators, MSCs have been widely utilized in the development of both cell-based and cell-free products (such as conditioned media and extracellular vesicles) for the treatment of various chronic inflammatory and autoimmune diseases [109]. In particular, promising preclinical and clinical results have been achieved in the treatment of rheumatoid arthritis [110,111], multiple sclerosis [112,113], type 1 diabetes [114,115,116], colitis [117,118], and other conditions. In the context of research on T1D therapy using MSCs and their secretome (exosomes, conditioned media), three main research directions can be identified: (1) MSCs as "chaperones" that support the engraftment of transplanted β-cells; (2) MSCs as stimulators of regeneration that exert a protective effect on β-cells; and (3) MSCs as immunomodulators that negatively regulate autoimmune processes.
Islet cell transplantation in T1D is an effective treatment strategy, and the outcomes of such procedures continue to improve each year. However, the isolation of human islets significantly impairs their functional activity. Moreover, following transplantation, they are exposed to a hostile microenvironment characterized by inflammation, hypoxia and elevated glucose levels, which substantially reduces their engraftment and survival [119,120]. Numerous studies have demonstrated that the co-transplantation of islets with MSCs significantly improves their engraftment and preserves functional activity, owing to the protective and immunomodulatory effects of the MSCs [121,122,123]. Furthermore, preconditioning islet cells with a cocktail of biologically active molecules secreted by MSCs has been shown to protect β-cells from inflammatory cytokine-induced apoptosis and enhance insulin secretion both in vitro and in vivo [124]. MSC-derived extracellular vesicles have also exerted a beneficial effect on the function and survival of pancreatic islet cells. They protect against apoptosis and enhance insulin secretion by delivering biologically active components to recipient cells, including C3, ANXA1, SDF-1/CXCL12, and microRNAs (such as miR-21a-5p) [125].
The regenerative and immunomodulatory properties of MSCs described above—including their ability to protect islet cells from apoptosis, stimulate angiogenesis, and suppress autoimmune aggression—provide a compelling theoretical rationale for the application of cell therapy in T1D. However, it is crucial to consider that following transplantation, MSCs are no longer in the controlled environment of a cell culture, but rather in the hostile internal milieu of the body, which is characterized by chronic hyperglycemia, oxidative stress, and systemic inflammation. Understanding how the diabetic microenvironment affects the viability, functional activity, and therapeutic potential of transplanted MSCs is a critical prerequisite for a realistic assessment of the prospects of this approach.
5. Transplanted MSCs in the Diabetic Microenvironment
After grafting, transplanted MSCs find themselves in an environment very different from cell culture conditions. Moreover, the parameters of this environment depend on the patient's clinical status. In patients with diabetes, elevated glucose concentrations in body fluids and tissues represent the primary hallmark of the internal milieu, which may affect the viability of transplanted cells and the overall efficacy of cell-based therapy. In healthy individuals, glucose levels are maintained within a narrow physiological range to ensure optimal uptake and utilization by all cells. For healthy young adults, the World Health Organization defines the reference range for fasting venous serum glucose as 3.9–5.5 mM [126]. For adults aged over 60 years, the recommended upper reference limit is 6.1 mM. Immediately after a meal, glucose concentrations rise and may double within 2 hours, after which they gradually return to baseline levels, occasionally reaching 12–13 mM. In the cerebrospinal fluid (CSF) of healthy adults, glucose concentration is 2.8–3.9 mM—lower than in plasma—due to the glucose concentration gradient between blood and brain parenchyma maintained by the blood–brain barrier [127]. Similar barriers regulating glucose uptake are also present in other tissues [128]. In untreated patients with diabetes, fasting serum glucose levels typically exceed 10 mM and may rise above 25 mM, but can be lowered with appropriate therapy. For patients with diabetes on glucose lowering therapy, the current target range for fasting serum glucose is 4.6–7.1 mM [126].
MSCs, like other cells, depend on a supply of nutrients, including glucose, which is essential for energy production. MSCs can be maintained in vitro in culture media with widely varying glucose concentrations. For example, DMEM, the most widely used commercially available MSC culture medium, was initially formulated with a glucose concentration of 5.6 mM, mimicking physiological plasma levels. Later, a high glucose formulation of DMEM containing 25 mM glucose was introduced. Culturing various cell types in high glucose DMEM and other high glucose media has been proposed as an in vitro model of diabetes [129]. It has been argued that, because of their highly glycolytic phenotype, MSCs require large amounts of glucose for normal growth in culture, are strongly dependent on glucose supply, and are sensitive to glucose depletion in the medium [130]. As discussed below, high glucose concentrations in culture medium affect MSCs in multiple ways, most of which are detrimental. The net effect depends on the MSC tissue source, oxygen supply, concentrations of other nutrients, and the overall experimental design.
One of the early papers reported a lack of an immediate impact of high glucose concentration on the proliferation and growth factor production of human bone marrow MSCs [131]. Other researchers, even earlier, demonstrated that low glucose medium enhances MSC colony formation and inhibits apoptosis in primary human bone marrow MSC cultures, while high glucose produces the opposite effects and induces senescence [132,133]. In addition, high glucose was reported to impair the differentiation potential of primary MSCs. Interestingly, both papers reported that high glucose enhanced the proliferation of MSCs immortalized by TERT. Later, Chang et al. [134] confirmed these results in primary MSCs and also demonstrated that high glucose activates autophagy. Both short- and long-term exposure of human BM-MSCs to high glucose inhibited proliferation and limited their adipogenic differentiation potential [135]. In contrast, endothelial progenitor cells were resistant to acute or chronic high glucose challenge.
Another study reported inhibition of proliferation, enhancement of adipogenic differentiation, and upregulation of several adipogenesis related genes in cultures of MSCs derived from human bone marrow and several gestational tissues—chorion, placenta, and umbilical cord [136]. Osteogenic differentiation remained unchanged, although several related genes were downregulated. Maintenance of human nucleus pulposus derived MSCs in high glucose medium resulted in decreased proliferation, colony formation, migration, and wound healing activity, along with increased apoptosis, senescence, and caspase 3 expression, as well as suppression of stemness related genes and downregulation of SIRT1, SIRT6, HIF 1α, and GLUT 1 at both the mRNA and protein levels [137]. Osteogenic differentiation of MSCs isolated from the buccal fat pad, as assessed by osteogenic marker expression, calcium deposition, and alkaline phosphatase activity, was significantly more pronounced in low glucose (5.5 mM) than in high glucose (25 mM) conditions [138]. The detrimental effects of high glucose were attenuated by the addition of platelet rich plasma. High glucose impairs mitochondrial function in human adipose derived MSCs by disrupting mitochondrial membrane potential and the NAD⁺/NADH pool, and also interferes with mTOR dependent regulatory pathways [139].
The studies cited above were carried out under normoxic conditions. Since energy production in MSCs is largely glycolytic, the response of MSCs to high glucose may differ under hypoxic conditions. Notably, an earlier study claimed that high glucose supports BM-MSCs survival and proliferation under severely hypoxic conditions [140]. However, the validity of this notion was never confirmed.
MSCs possess pronounced immunomodulatory activity, which is their most pivotal property from a translational perspective and the basis for many clinical applications currently in development. It has been shown that high glucose inhibits the immunomodulatory properties of human adipose derived MSCs and makes them more susceptible to immune recognition [141]. In this particular case, the decline in MSC immunosuppressive capacity may be attributed to reduced levels of IDO, IL-10, and complement factor H, along with increased immunoproteasome activity. High glucose downregulated levels of AMP activated protein kinase (AMPK) and phosphofructokinase 1 (PFK1), both of which regulate glycolysis. These findings may explain the poor survival of transplanted MSCs and the occasionally disappointing clinical outcomes of MSC based therapy in diabetic patients. This is consistent with reports showing toxic effects of hyperglycemia on human and rodent MSCs both in vitro and in vivo, possibly through modulation of the Wnt/β catenin, PI3K/Akt, MAPK, and PKC pathways, as well as through alterations in microRNA expression [142,143,144].
Manufacturing protocols for clinical grade cell generation in MSC based therapy for diabetes must be developed taking glucose concentration in the culture medium into account, since high glucose levels are likely to affect the properties of the generated cells by modifying long lived macromolecules through glycation and glyoxidation, which can lead to loss of function and oxidative stress [145,146,147]. Through this mechanism, cells may retain metabolic memory of prior exposure to high glucose even after several passages in low glucose medium or after transplantation. Several media widely used in biomanufacturing, such as DMEM (Hi), GMEM, and IMDM, contain diabetes relevant 25 mM D glucose levels, and it will probably be necessary to adjust the corresponding manufacturing protocols. Fortunately, in vitro effects of high glucose on MSCs may be at least partly reversible. Tan et al. [148] induced accelerated aging in human synovial MSC cultures by exposing them to high glucose medium (25 mM) for 24 hours and then returning them to normal glucose medium (5 mM) for an additional 24 hours. High glucose induced accelerated senescence, as evidenced by upregulation of senescence associated secretory phenotype (SASP) genes, an increased number of senescence associated β galactosidase (SA β gal) positive cells, elevated mitochondrial ROS levels, and enhanced mitochondrial fission. These effects were largely reversed by subsequent incubation in low glucose medium for 24 hours.
Thus, the diabetic microenvironment can substantially limit the therapeutic efficacy of MSCs, a consideration that is critical for interpreting preclinical studies where cell therapy is tested directly in experimental diabetes. Animal models that recapitulate key T1D pathogenetic features are essential for assessing how well MSCs retain their protective and immunomodulatory potential under conditions of hyperglycemia and autoimmune inflammation, and for identifying optimal delivery, dosing, and cell modification strategies to counteract the deleterious effects of the diabetic environment.
6. Preclinical Assessment of MSC-Based Immunotherapy in T1D Animal Models
The most frequently used mouse models suitable for studying T1D are non-obese diabetic (NOD) mice, in which the disease develops spontaneously [149]. Alternatively, T1D is induced via intraperitoneal injections of streptozotocin or alloxan [150]. In various animal models of T1D, MSC transplantation has been shown to exert a protective effect on the cells of deteriorating islets by reducing cell death, restoring glycemic levels, enhancing islet cell proliferation, and stimulating their endogenous regeneration [151]. In their study, Gao et al. [152] demonstrated that MSCs modified to overexpress SPARC (secreted protein acidic and rich in cysteine) and administered intravenously to mice with streptozotocin-induced T1D significantly reduced hyperglycemia, gradually ameliorated pancreatic islet damage, and promoted the recovery of β-cell function and insulin production. SPARC regulates β-cell survival, and its overexpression in β-cells cultured under high-glucose conditions enhances insulin secretion [153,154]. Exosomes derived from MSCs and loaded with nanoselenium also exerted a protective effect in the streptozotocin-induced T1D model. They substantially reduced oxidative stress in the islets, increased intracellular antioxidant levels, markedly suppressed islet cell apoptosis (thereby increasing their viability), and restored islet architecture [155]. Some studies have shown that MSC-derived exosomes can slow down or even halt the progression of T1D by inhibiting the autoimmune destruction of pancreatic β-islets, promoting the apoptosis of autoreactive T cells and the proliferation of Tregs. This leads to enhanced islet regeneration, angiogenesis, and survival, ultimately increasing insulin secretion and controlling hyperglycemia and its complications [156,157]. Furthermore, results have been described demonstrating that the protective and regenerative properties of MSC-derived exosomes can lead to the functional restoration of existing islets [154,158]. In addition to their effects on pancreatic islets and the restoration of β-cell functional activity, MSC transplantation also leads to at least partial recovery of other organs damaged during T1D progression, including the liver, kidneys, and spleen [159].
The most extensive body of published literature consists of studies investigating the immunomodulatory role of MSCs in animal models of T1D. Preclinical studies have shown that MSCs can slow down or even reverse the progression of diabetes in non-obese diabetic (NOD) mice [160,161]. The primary mechanism involves the modulation of autoimmune reactions against the islets of Langerhans. In addition to suppressing pathogenic CD8⁺ T cells, Th1, and Th17 cells [162,163], MSCs can also promote the expansion of Tregs through paracrine effects, direct interaction with cellular receptors, or mitochondrial transfer [164]. For instance, Zhang et al. [165], comparing the therapeutic efficacy of bone marrow-derived and umbilical cord MSCs (hUC-MSCs) administered intravenously to NOD mice with streptozotocin-induced T1D, showed that the main mechanism underlying MSC-mediated T1D remission is primarily related to the modulation of autoimmune islet destruction. Both cell types significantly attenuated insulitis in the islets, reduced the number of Th17 cells (IL-17⁺CD4⁺), and increased the number of Tregs (FOXP3⁺CD4⁺) in the spleen and lymph nodes [163]. An increase in the number of Tregs was also observed in rats with streptozotocin-induced T1D following the intraperitoneal injection of conditioned media obtained from hUC-MSCs cultured in 2D and 3D conditions [166]. Wu et al. [167] found that the TGFBI gene is essential for the immunomodulatory function of hUC-MSCs in the streptozotocin-induced T1D mouse model. Following intravenous administration, hUC-MSCs with low TGFBI expression exhibited reduced immunosuppressive capacity and a weakened therapeutic effect, manifested by increased pathological islet damage, a higher number of infiltrating T cells in the pancreas, and increased expression of IFN-γ and IL-17A. Conversely, TGFBI produced by hUC-MSCs suppressed the proliferation of activated T cells by inhibiting Cyclin D2 expression. TGFBI is an extracellular matrix protein that plays a vital role in ensuring the survival and function of the islets of Langerhans and in inhibiting T-cell activation [168,169]. The important role of TGF-β in the immunomodulation mediated by transplanted MSCs in the streptozotocin-induced diabetes mouse model was also demonstrated by Du et al. [170], who established that 3D culture of umbilical cord MSCs triggers their transcriptomic reprogramming toward a YAP1 state activated by the Hippo signaling pathway, accompanied by enhanced release of TGF-β1 [168].
Lachaud et al. [171], using the RIP-B7.1 mouse model of experimental autoimmune diabetes induced by injection of a preproinsulin (ppINS) expression plasmid—a model that accurately mimics the aggressive immune attack observed in young children with T1D [172]—showed that intraperitoneal injection of umbilical cord MSCs led to a pronounced recruitment of myeloid-derived suppressor cells (MDSCs) into the peritoneal cavity. This was followed by multiple immunosuppressive responses of T, B, and myeloid cells in the peritoneal fluid, spleen, pancreatic lymph nodes, and pancreas, resulting in a significant reduction in insulitis and pancreatic infiltration by T and B cells, as well as pro-inflammatory macrophages. A single dose of UC-MSCs provided the best protection against the development of insulitis, preserved islet integrity and normal α- and β-cell content, reduced plasma concentrations of pro-inflammatory cytokines IL-6, IFN-γ, and TNF-α, and resulted in significantly fewer CD4⁺ and CD8⁺ T cells, CD19⁺ B cells, and CD11b⁺ myeloid cells infiltrating the pancreas. A notable finding in this study is that UC-MSCs transplanted into RIP-B7.1 mice were massively exposed to CD11b^high peritoneal macrophages, leading to the formation of peritoneal UC-MSC/macrophage aggregates, which were eliminated from the abdominal cavity via phagocytosis [168]. Despite their rapid clearance from the body, the transplanted UC-MSCs significantly altered the cellular composition and inflammatory state of resident immune cells in the peritoneal fluid, triggering a rapid and massive mobilization of CD11b^med/Ly6C^+/-^hi MDSCs into the peritoneal cavity, which play a critical role in the resolution of acute inflammation [173]. Furthermore, UC-MSC transplantation caused a significant increase in the expression of arginase I (ARG1) in the peritoneal fluid. ARG1 is an enzyme with potent immunosuppressive activity, highly expressed by mouse MDSCs and anti-inflammatory M2 macrophages during the resolution phase of inflammation [174,175]. The next stage in the development of the anti-inflammatory response to UC-MSC administration, as observed by the authors, was the intraperitoneal mobilization of Tregs, as well as their expansion in the pancreatic lymph nodes and spleen. Thus, UC-MSCs induced several waves of immune responses, shifting their aggressive autoreactive nature toward an anti-inflammatory and regenerative profile.
In addition to umbilical cord and adipose MSCs, which are the most frequently investigated in the context of T1D therapy [176], MSCs derived from other tissue sources also demonstrate pronounced immunomodulatory effects. These include MSCs from the outer root sheath of the hair follicle [177], menstrual blood-derived endometrial MSCs [157], and others.
To enhance the immunomodulatory properties of MSCs in the context of diabetes therapy and other immune-mediated diseases, preconditioning is often applied. For example, direct conditioning of MSCs via hypoxia, treatment with IFN-γ, poly(I:C), or LPS has been shown to significantly increase the immunomodulatory activity of both the cells themselves and their derived extracellular vesicles in the streptozotocin-induced T1D mouse model [178,179]. 3D culture or culturing MSCs as cellular aggregates on low-adhesion plastic promotes the enhancement of the cells' immunomodulatory properties and a much greater production of extracellular vesicles, which also possess more pronounced immunomodulatory effects [180,181]. Ren et al. [182] demonstrated that extracellular vesicles derived from aggregated MSCs inherit lactate from the parent cells and, upon being taken up by CD8⁺ T cells, enhance L-cysteine breakdown within them. Consequently, L-cysteine metabolism is upregulated in CD8⁺ T cells, leading to decreased levels of L-cysteine, glutathione (GSH), and the GSH/GSSG (glutathione disulfide) ratio, which in turn results in increased hydrogen sulfide (H2S) levels. H2S can activate β-catenin, increasing the expression of programmed cell death protein 1 (PD-1) and thereby suppressing the proliferation and function of CD8⁺ T cells. When administered to animals with T1D, such extracellular vesicles led to the depletion of the CD8⁺ T-cell pool and improved indicators of β-cell functional activity [180].
Thus, based on the preclinical results of T1D therapy using MSCs, it can be concluded that significant progress has been made in this field over the past decade. At the very least, many of the mechanisms underlying the therapeutic effects of MSCs are now known, and methods to enhance these effects have been developed. Over time, all these findings may form the basis for the development of the most effective cell-based or cell-free products for the treatment of this disease.
7. Clinical Studies of Immunomodulatory Therapy with MSCs in T1D
Extensive preclinical studies in animal models of T1D have demonstrated that MSCs not only support β-cell survival but also actively modulate the pathogenic cascade: suppressing islet infiltration, mitigating local inflammation, and promoting peripheral tolerance. These findings have laid the foundation for translating MSC-based therapies into clinical practice. Clinical trials of MSC-based immunomodulatory therapy in T1D began more than a decade ago and remain ongoing. This evolution reflects a shift from attempts to induce pancreatic β-cell regeneration toward immunomodulatory strategies aimed at suppressing the autoimmune attack and preserving residual β-cell function.
An analysis of registered on ClinicalTrials.gov protocols [183] and published research articles reveals significant design heterogeneity (Table 2). The studies employ MSCs from various autologous and allogeneic tissues: bone marrow, adipose tissue, umbilical cord including Wharton's jelly. Administration strategies range from single infusions to multiple courses as well as dose-escalation designs. Most protocols use systemic intravenous administration, which ensures cell migration to sites of inflammation via chemokine gradients. There are attempts to employ targeted super selective intra-arterial infusion directly into the pancreatic artery to maximize the localization of the cellular product in the zone of active infiltration and destruction of the islets of Langerhans.
In recent decades, the mechanism of action of MSCs has undergone a key conceptual shift: from the belief in their ability to trans-differentiate into insulin-producing cells toward systemic and local immunomodulation. In most of the analyzed protocols, the immunomodulatory effect is declared as the primary hypothesis or included in the key endpoints. It is hypothesized that MSCs secrete a wide range of paracrine factors (IDO, PGE₂, TGF-β, IL-10, exosomes with regulatory miRNAs) that induce macrophage polarization from the pro-inflammatory M1 phenotype to the anti-inflammatory M2 phenotype, suppress the proliferation of effector Th1/Th17 lymphocytes, and promote the expansion of CD4⁺FoxP3⁺ Tregs. Even in the absence of direct β-cell regeneration, the creation of a local immunosuppressive microenvironment in the islets of Langerhans and pancreatic lymph nodes allows for the interruption of the pathogenic cascade of autoimmune aggression and the preservation of residual pancreatic function.
The analyzed parameters demonstrate clear stratification. Standard metabolic and clinical markers are universally used across all studies: C-peptide levels (basal and stimulated after MMTT/OGTT), glycated hemoglobin (HbA1c), daily exogenous insulin requirement, frequency of hypoglycemic events, and safety profile (recording of adverse events). Less frequently, but with a clear focus on pathophysiology, protocols include specific immunological and technologically complex indicators: islet autoantibody titers (GAD65, IA-2, ZnT8), lymphocyte subpopulation phenotyping (Treg/Th17 ratio, direct measurement of CD4⁺FoxP3⁺), cytokine profiles, and continuous glucose monitoring (CGM) data with calculated variability indices. Some studies extend beyond short-term follow-ups, evaluating long-term microvascular complications over 5–8 years, which sets a new horizon for assessing the durability of the therapeutic effect.
Although most studies are in the recruitment or protocol planning stages, a number of published works provide verified clinical data confirming the therapeutic potential of MSCs in T1D. A general trend is a significant reduction in the need for exogenous insulin and improved glycemic control within the first few months after administration, which is accompanied by a prolongation of the partial remission phase ("honeymoon period") in the vast majority of patients in the therapy groups. By the six-month follow-up, a significant increase in basal C-peptide is recorded, indicating the preservation of functional activity of residual β-cells. In cohorts with severe disease onset, including diabetic ketoacidosis, comparable efficacy of umbilical cord and bone marrow MSCs has been demonstrated. This is supported by both clinical and parallel preclinical data showing identical reductions in insulitis, a decrease in the Th17 lymphocyte pool, and an increase in Tregs. Randomized trials confirm that stimulated C-peptide is maintained or increased in the therapy groups, whereas the expected progressive loss of β-cell function occurs in the control groups; meanwhile, no serious therapy-related adverse events have been reported. The most indicative long-term data, with follow-up of up to eight years, show that combination therapy with targeted intra-arterial delivery provided not only sustained improvement in metabolic parameters in the first year but also a statistically significant reduction in the incidence of microvascular complications—peripheral neuropathy and diabetic nephropathy—compared to the control group. This indicates a prolonged immunometabolic effect that extends beyond short-term metabolic correction.
Of particular interest are the data from several studies indicating that the effects of MSC therapy in T1D may persist for prolonged periods. Clinical protocols generally do not involve extended treatment courses and are typically limited to one or several cell injections (Table 2). Nevertheless, therapeutic effects have been reported to persist throughout the entire follow-up period, in some cases for up to 7 years [184,185,186,187]. Given the short persistence of allogeneic MSCs in the recipient’s body demonstrated in animal models [188], the duration of these effects is remarkable and raises important questions regarding the mechanisms underlying the long-term therapeutic action of MSCs.
8. Therapeutic Potential of MSCs in Addressing Long-Term Complications of T1D
The risk of progressive damage to blood vessels, peripheral nerves, and kidneys (diabetic neuropathy, nephropathy, and retinopathy) remains substantially elevated in the long term, even when target metabolic goals are achieved. This is because insulin replacement therapy does not eliminate the chronic metabolic disturbances and systemic inflammation that underlie microvascular complications [189]. Exogenous insulin compensates for the hormone deficiency but does not suppress autoimmune activity or normalize the post-translational modifications of proteins that continue to drive endothelial dysfunction and axonal degeneration [190].
A key cross-reactive autoantigen linking pancreatic autoaggression to neurological damage is GAD65. In the pancreas, GAD65 is localized in the cytosol of β-cells, where it functions as an enzyme catalyzing the synthesis of γ-aminobutyric acid (GABA), and it serves as one of the primary targets of autoantibodies at the clinical onset of T1D [191]. Concurrently, GAD65 is expressed in GABAergic neurons of the central and peripheral nervous systems, where it acts as a key regulator of inhibitory processes and the maintenance of neurophysiological homeostasis [192]. This dual tissue localization is dictated by the evolutionarily conserved structure of the isoenzyme, rendering neurons vulnerable to cross-reactivity from antibodies initially formed against islet cells [193]. Current research confirms that the conformation-dependent GAD65 epitopes recognized in T1D are structurally homologous to GAD65 epitopes present on neurons. Due to this similarity, antibodies generated against pancreatic GAD65 can bind directly to neuronal GAD65 without requiring additional affinity maturation [194]. Under conditions of systemic inflammation, high-affinity anti-GAD65 antibodies can cross the blood-brain barrier and bind directly to GABAergic neurons, disrupting synaptic transmission and contributing to the development of cognitive impairment and autonomic dysfunction [195]. As the disease progresses, the autoimmune response broadens to adjacent epitopes and related neural proteins, which exponentially amplifies local neuroinflammation and accelerates axonal degeneration [196]. Recent data demonstrate that this process sequentially involves homologous neural proteins (including GAD67 and neurofilaments), which clinically correlates with the progression of neuropathy independent of current glycemic control [197]. Furthermore, a specific expansion of CD4⁺ T cells responding to GAD65 peptides with neuronal homology has been identified, definitively confirming molecular mimicry as a key mechanism of neuroimmune damage [198]. The accumulation of high-affinity antibodies promotes the formation of immune complexes, complement activation, and the recruitment of cytotoxic lymphocytes into the perineurium. This drives the development of systemic polyneuropathy, significantly impairing patients' quality of life and reducing their life expectancy [194].
Furthermore, the kidneys and retina are also targets of T1D-associated cross-reactive autoimmunity, where chronic inflammation and immune dysregulation play a role no less significant than metabolic disturbances. Despite advances in glycemic control, diabetic nephropathy and retinopathy remain the leading causes of end-stage renal disease and irreversible vision loss, indicating the existence of glycemia-independent pathogenic mechanisms [199]. The pathogenesis of diabetic nephropathy has traditionally been linked to hemodynamic disturbances; however, current data emphasize the role of immune infiltration in the glomeruli and tubules. In the renal tissue of patients with T1D, increased expression of pro-inflammatory cytokines (IL-1β, TNF-α, IL-6), chemokines (MCP-1), and infiltration by macrophages and T lymphocytes are observed, which correlates with the rate of decline in the glomerular filtration rate [200,201]. Although direct cross-reactivity of anti-GAD65 with renal antigens remains hypothetical, the general autoimmune background creates favorable conditions for the progression of nephropathy, independent of the level of glycemic control [199].
Similar mechanisms are observed in the pathogenesis of diabetic retinopathy. In addition to classical factors (oxidative stress, protein kinase C activation, accumulation of advanced glycation end products), dysfunction of the blood-retinal barrier, mediated by the activation of resident microglia and infiltration by peripheral immune cells, plays a key role [202]. GAD65 is expressed in the amacrine and horizontal cells of the retina, where it participates in the GABAergic modulation of visual signals [203], theoretically rendering these structures vulnerable to cross-reactive antibody attacks. However, the direct pathogenic role of anti-GAD65 in the development of retinopathy remains hypothetical and requires further verification. It is well established that the systemic pro-inflammatory state in T1D (elevated levels of IL-6, TNF-α, MCP-1) promotes the progression of retinopathy independently of glycemic control [204]. Thus, persistent autoaggression initiated in the pancreas forms a unified pathogenic cascade that affects the nervous system, kidneys, and retina through common immunological mechanisms.
In this context, MSC therapy acquires a fundamentally new significance. Its immunomodulatory potential remains clinically relevant even in situations where the islet apparatus is completely destroyed, β-cells are absent, and the patient is entirely dependent on exogenous insulin [205]. MSCs systemically suppress autoaggressive clones, reduce titers of circulating anti-GAD65 antibodies, and block the neuroinflammation cascade through the paracrine secretion of IDO, PGE₂, TGF-β, and exosomes containing regulatory microRNAs [206]. Recent preclinical data expand this paradigm, demonstrating that MSCs can exert local effects on the peripheral nervous system: they secrete neurotrophic factors (BDNF, NGF, GDNF), suppress the activation of resident macrophages in the endoneurium, and stimulate axonal remyelination, with these effects persisting even after the complete loss of β-cell mass [207] (Figure 2).
Figure 2.
Mesenchymal Stromal Cells Target Multiple Pathological Processes in Type 1 Diabetes.
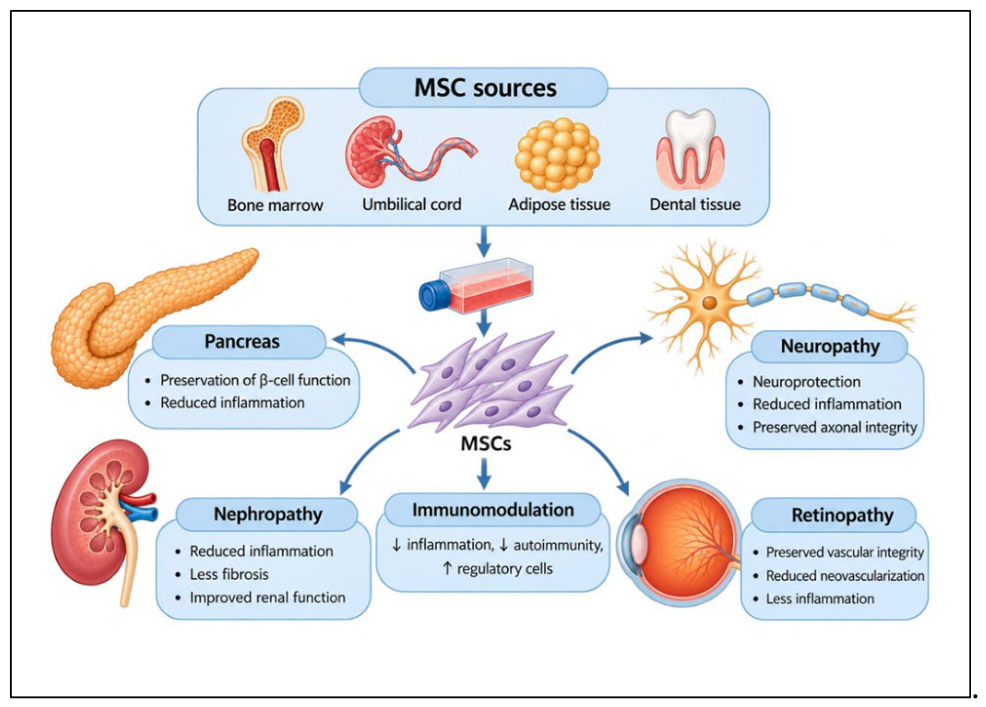
In the context of nephropathy, MSCs polarize macrophages from the pro-inflammatory M1 phenotype to the reparative M2 phenotype, reducing the production of fibrogenic cytokines (TGF-β1, CTGF) and slowing the development of glomerulosclerosis and tubulointerstitial fibrosis [208]. MSC-derived exosomes enriched with regulatory miRNAs (miR-146a, miR-21) suppress the activation of NF-κB and TGF-β/Smad pathways in mesangial cells, experimentally confirming the antifibrotic potential of cell therapy [209]. In retinopathy, MSCs demonstrate a dual effect: they suppress the pathological neovascular response (by inhibiting VEGF signaling under hyperglycemic conditions) while simultaneously maintaining the physiological integrity of the endothelium through the secretion of angiopoietin-1 and survival factors [210]. Furthermore, the well-known immunomodulatory properties of MSCs—reducing pro-inflammatory cytokine levels (IL-6, TNF-α), polarizing macrophages toward the anti-inflammatory M2 phenotype, and expanding Tregs — create a favorable systemic background that could theoretically and indirectly slow the progression of retinopathy [204,206]. However, a direct causal link between systemic MSC immunomodulation and a specific protective effect on kidney and retinal tissues in T1D remains hypothetical and requires further experimental and clinical verification. Critically, the described mechanisms do not require the differentiation of MSCs into renal or neuronal cells. The therapeutic effect is realized through paracrine regulation of the microenvironment, making this therapy applicable even in the late stages of complications, when structural tissue restoration is biologically impossible.
9. Conclusions
MSCs represent one of the most promising platforms for cell therapy in T1D, capable of targeting key nodes of the autoimmune cascade—from antigen presentation and effector T-cell activation to the sustenance of chronic inflammation in the islets of Langerhans.
The immunopathogenic rationale for using MSCs is grounded in their proven ability to modulate both innate and adaptive immunity via the paracrine secretion of anti-inflammatory mediators, the induction of macrophage polarization, and the expansion of Tregs. In preclinical models, this consistently results in reduced islet destruction, preservation of β-cell mass, and improved glycemic control. Although the number of completed clinical trials remains limited, they demonstrate consistent trends toward efficacy: prolongation of the partial remission phase, preservation of stimulated C-peptide levels, reduced exogenous insulin requirements, and, most notably, a decreased incidence of long-term microvascular complications during extended follow-up.
However, the translation of MSC therapy from experimental research into standard clinical practice is hindered by several fundamental and practical limitations. Analysis of the diabetic microenvironment's impact on transplanted cells has revealed that chronic hyperglycemia can suppress the immunomodulatory activity of MSCs, induce their premature senescence, and establish a "metabolic memory" that persists even after the restoration of normoglycemic culture conditions. This calls into question the efficacy of autologous MSCs derived from patients with decompensated diabetes and underscores the need to modify cell manufacturing protocols, including strict glucose control in culture media and preconditioning of cells to mimic target physiological environments. Furthermore, the high heterogeneity of cell products—regarding tissue source, dosage, cell passage, administration route, and infusion frequency—complicates standardization and the conduct of comparable meta-analyses. Currently, the absence of large, multicenter, phase III randomized controlled trials precludes the formulation of definitive clinical guidelines.
A fundamentally important question concerns the specificity of the immunomodulatory action of MSCs: do they selectively suppress cross-reactive autoreactive lymphocyte clones, or do they exert a broad, non-specific anti-inflammatory effect, and how does this impact the long-term safety of the therapy? The optimal parameters for cell therapy aimed at protecting against microangiopathies may differ from those required for modulating islet autoimmunity, necessitating a tailored approach to the choice of MSC source, delivery route, and dosing regimen based on the specific clinical objective. Successful translation will require the implementation of validated biomarkers for patient selection, the standardization of cell products with a view toward transitioning to cell-free exosomal platforms, and the mandatory inclusion of immunological endpoints in the design of future randomized trials. A particularly promising direction is the integration of MSC therapy with low-dose interleukin-2 or antigen-specific tolerogenic vaccines to create a synergistic immunomodulatory profile aimed at establishing durable peripheral tolerance.
If future research confirms that MSCs can interrupt the cascade of autoimmune damage to peripheral nerves, kidneys, and the retina—even after the complete loss of pancreatic endocrine function—this will open a fundamentally new therapeutic niche for patients with long-standing disease, for whom traditional approaches have proven ineffective. Shifting the paradigm from β-cell regeneration to the systemic immunomodulation of long-term complications has the potential not only to prolong the lives of patients with T1D but also to significantly improve their quality of life. By preventing blindness, end-stage renal disease, and disabling neuropathy, this approach could address the primary determinants of mortality and morbidity associated with the disease.
Ultimately, the therapeutic potential of MSCs in T1D, driven by their diverse immunomodulatory properties, can be fully realized only by deepening our fundamental understanding and expanding the preclinical evidence base. This will enable the field to overcome existing limitations, develop high-quality, standardized cell products, and successfully translate them into routine clinical practice.
Author Contributions
Conceptualization, A.L. and K.Y.; methodology, K.Y.; investigation, A.L., I.P., I.K and K.L.; data curation, R.K. and I.M.; writing—original draft preparation, A.L., I.P., I.K., K.Y; writing—review and editing, all authors; supervision, M.S., V.C. and N.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research was supported by the Ministry of Science and Higher Education of the Russian Federation (Agreement no. 075-15-2024-645).
Data Availability Statement
Not applicable.
Acknowledgments
Generative artificial intelligence (ChatGPT, OpenAI) was used to assist in the generation of selected schematic graphical elements used in the figures. The final figures were assembled in Microsoft PowerPoint, edited, and scientifically reviewed by the authors.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| The following abbreviations are used in this manuscript | . |
| CTLs | Cytotoxic T-lymphocytes |
| DCs | Dendritic cells |
| EVs | Extracellular Vesicles |
| GAD65 | Glutamic Acid Decarboxylase 65 |
| HLA | Human Leukocyte Antigen |
| HO-1 | Heme Oxygenase-1 |
| IA-2 | Insulinoma-Associated protein 2 |
| IDO1 | Indoleamine 2,3-dioxygenase |
| IFN | Interferon |
| IL | Interleukin |
| iNOS | inducible Nitric Oxide Synthase |
| MHC | Major Histocompatibility Complex |
| MSCs | Mesenchymal stromal cells |
| PGE2 | Prostaglandin E2 |
| ROS | Reactive Oxygen Species |
| T1D | Type 1 diabetes |
| Th0 | Naïve T-helper |
| TNF-α | Tumor Necrosis Factor alpha |
| tolDCs | Tolerogenic dendritic cells |
| Tregs | Regulatory T-cells |
| ZnT8 | Zinc Transporter 8 |
References
- Todd, J.A. Etiology of Type 1 Diabetes. Immunity 2010, 32, 457–467. [Google Scholar] [CrossRef] [PubMed]
- Bluestone, J.A.; Herold, K.; Eisenbarth, G. Genetics, Pathogenesis and Clinical Interventions in Type 1 Diabetes. Nature 2010, 464, 1293–1300. [Google Scholar] [CrossRef] [PubMed]
- Holt, R.I.G.; DeVries, J.H.; Hess-Fischl, A.; Hirsch, I.B.; Kirkman, M.S.; Klupa, T.; Ludwig, B.; Nørgaard, K.; Pettus, J.; Renard, E.; et al. The Management of Type 1 Diabetes in Adults: A Consensus Report by the American Diabetes Association (ADA) and the European Association for the Study of Diabetes (EASD). Diabetologia 2021, 64, 2609–2652. [Google Scholar] [CrossRef] [PubMed]
- Atkinson, M.A.; Eisenbarth, G.S.; Michels, A.W. Type 1 Diabetes. Lancet 2014, 383, 69–82. [Google Scholar] [CrossRef] [PubMed]
- Battelino, T.; Danne, T.; Bergenstal, R.M.; Amiel, S.A.; Beck, R.; Biester, T.; Bosi, E.; Buckingham, B.A.; Cefalu, W.T.; Close, K.L.; et al. Clinical Targets for Continuous Glucose Monitoring Data Interpretation: Recommendations from the International Consensus on Time in Range. Diabetes Care 2019, 42, 1593–1603. [Google Scholar] [CrossRef] [PubMed]
- The Writing Team for the Diabetes Control and Complications Trial/Epidemiology of Diabetes Interventions and Complications Research Group. Effect of Intensive Therapy on the Microvascular Complications of Type 1 Diabetes Mellitus. JAMA 2002, 287, 2563–2569. [CrossRef] [PubMed]
- The Diabetes Control and Complications Trial Research Group. The Effect of Intensive Treatment of Diabetes on the Development and Progression of Long-Term Complications in Insulin-Dependent Diabetes Mellitus. N. Engl. J. Med. 1993, 329, 977–986. [CrossRef] [PubMed]
- Waldron-Lynch, F.; Herold, K.C. Immunomodulatory Therapy to Preserve Pancreatic β-Cell Function in Type 1 Diabetes. Nat. Rev. Drug Discov. 2011, 10, 439–452. [Google Scholar] [CrossRef] [PubMed]
- Herold, K.C.; Bundy, B.N.; Long, S.A.; Bluestone, J.A.; DiMeglio, L.A.; Dufort, M.J.; Gitelman, S.E.; Gottlieb, P.A.; Krischer, J.P.; Linsley, P.S.; et al. An Anti-CD3 Antibody, Teplizumab, in Relatives at Risk for Type 1 Diabetes. N. Engl. J. Med. 2019, 381, 603–613. [Google Scholar] [CrossRef] [PubMed]
- Pescovitz, M.D.; Greenbaum, C.J.; Krause-Steinrauf, H.; Becker, D.J.; Gitelman, S.E.; Goland, R.; Gottlieb, P.A.; Marks, J.B.; McGee, P.F.; Moran, A.M.; et al. Rituximab, B-Lymphocyte Depletion, and Preservation of Beta-Cell Function. N. Engl. J. Med. 2009, 361, 2143–2152. [Google Scholar] [CrossRef] [PubMed]
- Pescovitz, M.D.; Greenbaum, C.J.; Bundy, B.; Becker, D.J.; Gitelman, S.E.; Goland, R.; Gottlieb, P.A.; Marks, J.B.; Moran, A.; Raskin, P.; et al. B-Lymphocyte Depletion With Rituximab and β-Cell Function: Two-Year Results. Diabetes Care 2014, 37, 453–459. [Google Scholar] [CrossRef] [PubMed]
- Hartemann, A.; Bensimon, G.; Payan, C.A.; Jacqueminet, S.; Bourron, O.; Nicolas, N.; Fonfrede, M.; Rosenzwajg, M.; Bernard, C.; Klatzmann, D. Low-Dose Interleukin 2 in Patients with Type 1 Diabetes: A Phase 1/2 Randomised, Double-Blind, Placebo-Controlled Trial. Lancet Diabetes Endocrinol. 2013, 1, 295–305. [Google Scholar] [CrossRef] [PubMed]
- Rosenzwajg, M.; Churlaud, G.; Mallone, R.; Six, A.; Dérian, N.; Chaara, W.; Lorenzon, R.; Long, S.A.; Buckner, J.H.; Afonso, G.; et al. Low-Dose Interleukin-2 Fosters a Dose-Dependent Regulatory T Cell Tuned Milieu in T1D Patients. J. Autoimmun. 2015, 58, 48–58. [Google Scholar] [CrossRef] [PubMed]
- Giannoukakis, N.; Phillips, B.; Finegold, D.; Harnaha, J.; Trucco, M. Phase I (Safety) Study of Autologous Tolerogenic Dendritic Cells in Type 1 Diabetic Patients. Diabetes Care 2011, 34, 2026–2032. [Google Scholar] [CrossRef] [PubMed]
- Ríos-Ríos, W.d.J.; Sosa-Luis, S.A.; Torres-Aguilar, H. Current Advances in Using Tolerogenic Dendritic Cells as a Therapeutic Alternative in the Treatment of Type 1 Diabetes. World J. Diabetes 2021, 12, 603–615. [Google Scholar] [CrossRef] [PubMed]
- Marek-Trzonkowska, N.; Myśliwiec, M.; Dobyszuk, A.; Grabowska, M.; Techmańska, I.; Juścińska, J.; Wujtewicz, M.A.; Witkowski, P.; Młynarski, W.; Balcerska, A.; et al. Administration of CD4+CD25highCD127− Regulatory T Cells Preserves β-Cell Function in Type 1 Diabetes in Children. Diabetes Care 2012, 35, 1817–1820. [Google Scholar] [CrossRef] [PubMed]
- Bettini, M.; Bettini, M.L. Function, Failure, and the Future Potential of Tregs in Type 1 Diabetes. Diabetes 2021, 70, 1211–1219. [Google Scholar] [CrossRef] [PubMed]
- Serr, I.; Drost, F.; Schubert, B.; Daniel, C. Antigen-Specific Treg Therapy in Type 1 Diabetes—Challenges and Opportunities. Front. Immunol. 2021, 12, 712870. [Google Scholar] [CrossRef] [PubMed]
- Giannoukakis, N. Tolerogenic Dendritic Cells in Type 1 Diabetes: No Longer a Concept. Front. Immunol. 2023, 14, 1212641. [Google Scholar] [CrossRef] [PubMed]
- Ray, S.; Palui, R. Immunotherapy in Type 1 Diabetes: Novel Pathway to the Future Ahead. World J. Diabetes 2024, 15, 2022–2035. [Google Scholar] [CrossRef] [PubMed]
- Shi, Y.; Wang, Y.; Li, Q.; Liu, K.; Hou, J.; Shao, C.; Wang, Y. Immunoregulatory Mechanisms of Mesenchymal Stem and Stromal Cells in Inflammatory Diseases. Nat. Rev. Nephrol. 2018, 14, 493–507. [Google Scholar] [CrossRef] [PubMed]
- Aggarwal, S.; Pittenger, M.F. Human Mesenchymal Stem Cells Modulate Allogeneic Immune Cell Responses. Blood 2005, 105, 1815–1822. [Google Scholar] [CrossRef] [PubMed]
- Corcione, A.; Benvenuto, F.; Ferretti, E.; Giunti, D.; Cappiello, V.; Cazzanti, F.; Risso, M.; Gualandi, F.; Mancardi, G.L.; Pistoia, V.; Uccelli, A. Human Mesenchymal Stem Cells Modulate B-Cell Functions. Blood 2006, 107, 367–372. [Google Scholar] [CrossRef] [PubMed]
- Németh, K.; Leelahavanichkul, A.; Yuen, P.S.; Mayer, B.; Parmelee, A.; Doi, K.; Robey, P.G.; Leelahavanichkul, K.; Koller, B.H.; Brown, J.M.; et al. Bone Marrow Stromal Cells Attenuate Sepsis via Prostaglandin E2-Dependent Reprogramming of Host Macrophages to Increase Their Interleukin-10 Production. Nat. Med. 2009, 15, 42–49. [Google Scholar] [CrossRef] [PubMed]
- Prockop, D.J.; Oh, J.Y. Mesenchymal Stem/Stromal Cells (MSCs): Role as Guardians of Inflammation. Mol. Ther. 2012, 20, 14–20. [Google Scholar] [CrossRef] [PubMed]
- Le Blanc, K.; Frassoni, F.; Ball, L.; Locatelli, F.; Roelofs, H.; Lewis, I.; Lanino, E.; Sundberg, B.; Bernardo, M.E.; Remberger, M.; et al. Mesenchymal Stem Cells for Treatment of Steroid-Resistant, Severe, Acute Graft-versus-Host Disease: A Phase II Study. Lancet 2008, 371, 1579–1586. [Google Scholar] [CrossRef] [PubMed]
- Wang, D.; Zhang, H.; Liang, J.; Li, X.; Feng, X.; Wang, H.; Hua, B.; Liu, B.; Lu, L.; Gilkeson, G.S.; et al. Allogeneic Mesenchymal Stem Cell Transplantation in Severe and Refractory Systemic Lupus Erythematosus: 4 Years of Experience. Cell Transplant. 2012, 22, 2267–2277. [Google Scholar] [CrossRef] [PubMed]
- Harris, V.K.; Stark, J.; Vyshkina, T.; Blackshear, L.; Joo, G.; Stefanova, V.; Sara, G.; Sadiq, S.A. Phase I Trial of Intrathecal Mesenchymal Stem Cell-Derived Neural Progenitors in Progressive Multiple Sclerosis. EBioMedicine 2018, 29, 23–30. [Google Scholar] [CrossRef] [PubMed]
- Chhabra, P.; Brayman, K.L. Stem Cell Therapy to Cure Type 1 Diabetes: From Hype to Hope. Stem Cells Transl. Med. 2013, 2, 328–336. [Google Scholar] [CrossRef] [PubMed]
- Li, L.; He, Y.; Zhao, J.; Yin, H.; Feng, X.; Fan, X.; Wu, W.; Lu, Q. Mesenchymal Stromal Cell-Based Therapy: A Promising Approach for Autoimmune Diseases. Clin. Rev. Allergy Immunol. 2025, 68, 21. [Google Scholar] [CrossRef] [PubMed]
- Maahs, D.M.; West, N.A.; Lawrence, J.M.; Mayer-Davis, E.J. Epidemiology of Type 1 Diabetes. Endocrinol. Metab. Clin. North Am. 2010, 39, 481–497. [Google Scholar] [CrossRef] [PubMed]
- Mobasseri, M.; Shirmohammadi, M.; Amiri, T.; Vahed, N.; Hosseini Fard, H.; Ghojazadeh, M. Prevalence and Incidence of Type 1 Diabetes in the World: A Systematic Review and Meta-Analysis. Health Promot. Perspect. 2020, 10, 98–115. [Google Scholar] [CrossRef] [PubMed]
- Patterson, C.C.; Dahlquist, G.G.; Gyürüs, E.; Green, A.; Soltész, G.; EURODIAB Study Group. Incidence Trends for Childhood Type 1 Diabetes in Europe During 1989–2003 and Predicted New Cases 2005–2020: A Multicentre Prospective Registration Study. Lancet 2009, 373, 2027–2033. [Google Scholar] [CrossRef] [PubMed]
- Diaz-Valencia, P.A.; Bougnères, P.; Valleron, A.-J. Global Epidemiology of Type 1 Diabetes in Young Adults and Adults: A Systematic Review. BMC Public Health 2015, 15, 255. [Google Scholar] [CrossRef] [PubMed]
- Leslie, R.D. Predicting Adult-Onset Autoimmune Diabetes: Clarity from Complexity. Diabetes 2010, 59, 330–331. [Google Scholar] [CrossRef] [PubMed]
- Ogle, G.D.; Wang, F.; Haynes, A.; Gregory, G.A.; King, T.W.; Deng, K.; Dabelea, D.; James, S.; Jenkins, A.J.; Li, X.; et al. Global Type 1 Diabetes Prevalence, Incidence, and Mortality Estimates 2025: Results from the International Diabetes Federation Atlas, 11th Edition, and the T1D Index Version 3.0. Diabetes Res. Clin. Pract. 2025, 225, 112277. [Google Scholar] [CrossRef] [PubMed]
- Gong, B.; Yang, W.; Xing, Y.; Lai, Y.; Shan, Z. Global, Regional, and National Burden of Type 1 Diabetes in Adolescents and Young Adults. Pediatr. Res. 2024, 97, 568–576. [Google Scholar] [CrossRef] [PubMed]
- International Diabetes Federation. IDF Diabetes Atlas 2025. Available online: https://diabetesatlas.org/resources/idf-diabetes-atlas-2025/ (accessed on 12 August 2026).
- Fang, M.; Wang, D.; Selvin, E. Prevalence of Type 1 Diabetes Among US Children and Adults by Age, Sex, Race, and Ethnicity. JAMA 2024, 331, 1411–1413. [Google Scholar] [CrossRef] [PubMed]
- Gregory, G.A.; Robinson, T.I.G.; Linklater, S.E.; Wang, F.; Colagiuri, S.; de Beaufort, C.; Donaghue, K.C. International Diabetes Federation Diabetes Atlas Type 1 Diabetes in Adults Special Interest Group Global Incidence, Prevalence, and Mortality of Type 1 Diabetes in 2021 with Projection to 2040: A Modelling Study. In Lancet Diabetes Endocrinol.; Magliano, D.J., Maniam, J., et al., Eds.; 2022; Volume 10, pp. 741–760. [Google Scholar] [CrossRef] [PubMed]
- Podar, T.; Solntsev, A.; Karvonen, M.; Padaiga, Z.; Brigis, G.; Urbonaite, B.; Viik-Kajander, M.; Reunanen, A.; Tuomilehto, J. Increasing Incidence of Childhood-Onset Type I Diabetes in 3 Baltic Countries and Finland 1983–1998. Diabetologia 2001, 44 (Suppl. 3), B17–B20. [Google Scholar] [CrossRef] [PubMed]
- Gillespie, K.M.; Bain, S.C.; Barnett, A.H.; Bingley, P.J.; Christie, M.R.; Gill, G.V.; Gale, E.A.M. The Rising Incidence of Childhood Type 1 Diabetes and Reduced Contribution of High-Risk HLA Haplotypes. Lancet 2004, 364, 1699–1700. [Google Scholar] [CrossRef] [PubMed]
- Steck, A.K.; Armstrong, T.K.; Babu, S.R.; Eisenbarth, G.S. Type 1 Diabetes Genetics Consortium. Stepwise or Linear Decrease in Penetrance of Type 1 Diabetes with Lower-Risk HLA Genotypes over the Past 40 Years. Diabetes 2011, 60, 1045–1049. [Google Scholar] [CrossRef] [PubMed]
- Dedov, I.I.; Shestakova, M.V.; Vikulova, O.K.; Zheleznyakova, A.V.; Isakov, M.A.; Sazonova, D.V.; Mokrysheva, N.G. Diabetes Mellitus in the Russian Federation: Dynamics of Epidemiological Indicators According to the Federal Diabetes Registry for the Period 2010–2022. Diabetes Mellit. 2023, 26, 104–123. [Google Scholar] [CrossRef]
- Shestakova, M.V.; Vikulova, O.K.; Zheleznyakova, A.V.; Isakov, M.A.; Dedov, I.I. Epidemiology of Diabetes Mellitus in the Russian Federation: What Has Changed over the Past Decade? Ther. Arch. 2019, 91, 4–13. [Google Scholar] [CrossRef] [PubMed]
- Sepe, V.; Loviselli, A.; Bottazzo, G.F. Genetics of Type 1A Diabetes. N. Engl. J. Med. 2009, 361, 211. [Google Scholar] [CrossRef] [PubMed]
- Dvoryanchikov, Y.V.; Minniakhmetov, I.R.; Laptev, D.N.; Khusainova, R.I.; Shestakova, M.V.; Mokrysheva, N.G. Genetic Predisposition to Autoimmune Diabetes Mellitus. Acta Naturae 2026, 18, 4–19. [Google Scholar] [CrossRef] [PubMed]
- Simmons, K.M.; Mitchell, A.M.; Alkanani, A.A.; McDaniel, K.A.; Baschal, E.E.; Armstrong, T.; Pyle, L.; Yu, L.; Michels, A.W. Failed Genetic Protection: Type 1 Diabetes in the Presence of HLA-DQB1*06:02. Diabetes 2020, 69, 1763–1769. [Google Scholar] [CrossRef] [PubMed]
- Minniakhmetov, I.; Yalaev, B.; Khusainova, R.; Bondarenko, E.; Melnichenko, G.; Dedov, I.; Mokrysheva, N. Genetic and Epigenetic Aspects of Type 1 Diabetes Mellitus: Modern View on the Problem. Biomedicines 2024, 12, 399. [Google Scholar] [CrossRef] [PubMed]
- Barrett, J.C.; Clayton, D.G.; Concannon, P.; Akolkar, B.; Cooper, J.D.; Erlich, H.A.; Julier, C.; Morahan, G.; Nerup, J.; Nierras, C.; et al. Genome-Wide Association Study and Meta-Analysis Find That Over 40 Loci Affect Risk of Type 1 Diabetes. Nat. Genet. 2009, 41, 703–707. [Google Scholar] [CrossRef] [PubMed]
- Bottini, N.; Musumeci, L.; Alonso, A.; Rahmouni, S.; Nika, K.; Rostamkhani, M.; MacMurray, J.; Meloni, G.F.; Lucarelli, P.; Pellecchia, M.; et al. A Functional Variant of Lymphoid Tyrosine Phosphatase Is Associated with Type I Diabetes. Nat. Genet. 2004, 36, 337–338. [Google Scholar] [CrossRef] [PubMed]
- Ueda, H.; Howson, J.M.M.; Esposito, L.; Heward, J.; Snook, H.; Chamberlain, G.; Rainbow, D.B.; Hunter, K.M.; Smith, A.N.; Di Genova, G.; et al. Association of the T-Cell Regulatory Gene CTLA4 with Susceptibility to Autoimmune Disease. Nature 2003, 423, 506–511. [Google Scholar] [CrossRef] [PubMed]
- Tang, W.; Cui, D.; Jiang, L.; Zhao, L.; Qian, W.; Long, S.A.; Xu, K. Association of Common Polymorphisms in the IL2RA Gene with Type 1 Diabetes: Evidence of 32,646 Individuals from 10 Independent Studies. J. Cell. Mol. Med. 2015, 19, 2481–2488. [Google Scholar] [CrossRef] [PubMed]
- Yeung, W.-C.G.; Rawlinson, W.D.; Craig, M.E. Enterovirus Infection and Type 1 Diabetes Mellitus: Systematic Review and Meta-Analysis of Observational Molecular Studies. BMJ 2011, 342, d35. [Google Scholar] [CrossRef] [PubMed]
- Hyöty, H. Viruses in Type 1 Diabetes. Pediatr. Diabetes 2016, 17 (Suppl. 22), 56–64. [Google Scholar] [CrossRef] [PubMed]
- Siljander, H.; Honkanen, J.; Knip, M. Microbiome and Type 1 Diabetes. EBioMedicine 2019, 46, 512–521. [Google Scholar] [CrossRef] [PubMed]
- Vatanen, T.; de Beaufort, C.; Marcovecchio, M.L.; Overbergh, L.; Brunak, S.; Peakman, M.; Mathieu, C.; Knip, M.; INNODIA Consortium. Gut Microbiome Shifts in People with Type 1 Diabetes Are Associated with Glycaemic Control: An INNODIA Study. Diabetologia 2024, 67, 1930–1942. [Google Scholar] [CrossRef] [PubMed]
- Writing Group for the TRIGR Study Group; Knip, M.; Åkerblom, H.K.; Al Taji, E.; Becker, D.; Bruining, J.; Castano, L.; Danne, T.; de Beaufort, C.; Dosch, H.-M.; et al. Effect of Hydrolyzed Infant Formula vs Conventional Formula on Risk of Type 1 Diabetes: The TRIGR Randomized Clinical Trial. JAMA 2018, 319, 38–48. [Google Scholar] [CrossRef] [PubMed]
- Uusitalo, U.; Lee, H.-S.; Aronsson, C.A.; Vehik, K.; Yang, J.; Hummel, S.; Silvis, K.; Lernmark, Å.; Rewers, M.; Hagopian, W.; et al. Early Infant Diet and Islet Autoimmunity in the TEDDY Study. Diabetes Care 2018, 41, 522–530. [Google Scholar] [CrossRef] [PubMed]
- Pugliese, A.; Zeller, M.; Fernandez, A., Jr.; Zalcberg, L.J.; Bartlett, R.J.; Ricordi, C.; Pietropaolo, M.; Eisenbarth, G.S.; Bennett, S.T.; Patel, D.D. The Insulin Gene Is Transcribed in the Human Thymus and Transcription Levels Correlated with Allelic Variation at the INS VNTR-IDDM2 Susceptibility Locus for Type 1 Diabetes. Nat. Genet. 1997, 15, 293–297. [Google Scholar] [CrossRef] [PubMed]
- Buckner, J.H. Mechanisms of Impaired Regulation by CD4(+)CD25(+)FOXP3(+) Regulatory T Cells in Human Autoimmune Diseases. Nat. Rev. Immunol. 2010, 10, 849–859. [Google Scholar] [CrossRef] [PubMed]
- Zirpel, H.; Roep, B.O. Islet-Resident Dendritic Cells and Macrophages in Type 1 Diabetes: In Search of Bigfoot's Print. Front. Endocrinol. 2021, 12, 666795. [Google Scholar] [CrossRef] [PubMed]
- Nakayama, M.; Simmons, K.M.; Michels, A.W. Molecular Interactions Governing Autoantigen Presentation in Type 1 Diabetes. Curr. Diabetes Rep. 2015, 15, 113. [Google Scholar] [CrossRef] [PubMed]
- Fucikova, J.; Palova-Jelinkova, L.; Bartunkova, J.; Spisek, R. Induction of Tolerance and Immunity by Dendritic Cells: Mechanisms and Clinical Applications. Front. Immunol. 2019, 10, 2393. [Google Scholar] [CrossRef] [PubMed]
- Mitchell, A.M.; Alkanani, A.A.; McDaniel, K.A.; Pyle, L.; Waugh, K.; Steck, A.K.; Nakayama, M.; Yu, L.; Gottlieb, P.A.; Rewers, M.J.; Michels, A.W. T-Cell Responses to Hybrid Insulin Peptides Prior to Type 1 Diabetes Development. Proc. Natl. Acad. Sci. USA 2021, 118, e2019129118. [Google Scholar] [CrossRef] [PubMed]
- Baker, R.L.; Jamison, B.L.; Wiles, T.A.; Lindsay, R.S.; Barbour, G.; Bradley, B.; Delong, T.; Friedman, R.S.; Nakayama, M.; Haskins, K. CD4 T Cells Reactive to Hybrid Insulin Peptides Are Indicators of Disease Activity in the NOD Mouse. Diabetes 2018, 67, 1836–1846. [Google Scholar] [CrossRef] [PubMed]
- Morgan, N.N.; Tse, H.M. NADPH-Derived Superoxide Influences CD4 T Cell Activation by Oxidizing Membrane Thiols. J. Immunol. 2016, 196 (Suppl. 1), 118.2. [Google Scholar] [CrossRef]
- Srivastava, N.; Vomund, A.N.; Yu, R.; Peterson, O.J.; Yang, Y.; Turicek, D.P.; Abousaway, O.; Li, T.; Kain, L.; Stone, P.; et al. A Microenvironment-Driven HLA-II-Associated Insulin Neoantigen Elicits Persistent Memory T Cell Activation in Diabetes. Nat. Immunol. 2026, 27, 82–97. [Google Scholar] [CrossRef] [PubMed]
- Zou, A.J.; Wan, X. From Disposal to Display: Crinophagy as a β-Cell Source of Neoantigens in Type 1 Diabetes. Immunol. Rev. 2026, 341, e70156. [Google Scholar] [CrossRef] [PubMed]
- Tersey, S.A.; Nishiki, Y.; Templin, A.T.; Cabrera, S.M.; Stull, N.D.; Colvin, S.C.; Evans-Molina, C.; Rickus, J.L.; Maier, B.; Mirmira, R.G. Islet β-Cell Endoplasmic Reticulum Stress Precedes the Onset of Type 1 Diabetes in the Nonobese Diabetic Mouse Model. Diabetes 2012, 61, 818–827. [Google Scholar] [CrossRef] [PubMed]
- Mannering, S.I.; Rubin, A.F.; Wang, R.; Bhattacharjee, P. Identifying New Hybrid Insulin Peptides (HIPs) in Type 1 Diabetes. Front. Immunol. 2021, 12, 667870. [Google Scholar] [CrossRef] [PubMed]
- Thomas, H.E.; McKenzie, M.D.; Angstetra, E.; Campbell, P.D.; Kay, T.W.H. Beta Cell Apoptosis in Diabetes. Apoptosis 2009, 14, 1389–1404. [Google Scholar] [CrossRef] [PubMed]
- Zhao, Y.; Scott, N.A.; Quah, H.S.; Krishnamurthy, B.; Bond, F.; Loudovaris, T.; Mannering, S.I.; Kay, T.W.H.; Thomas, H.E. Mouse Pancreatic Beta Cells Express MHC Class II and Stimulate CD4(+) T Cells to Proliferate. Eur. J. Immunol. 2015, 45, 2494–2503. [Google Scholar] [CrossRef] [PubMed]
- Russell, M.A.; Redick, S.D.; Blodgett, D.M.; Richardson, S.J.; Leete, P.; Krogvold, L.; Dahl-Jørgensen, K.; Bottino, R.; Brissova, M.; Spaeth, J.M.; et al. HLA Class II Antigen Processing and Presentation Pathway Components Demonstrated by Transcriptome and Protein Analyses of Islet β-Cells from Donors with Type 1 Diabetes. Diabetes 2019, 68, 988–1001. [Google Scholar] [CrossRef] [PubMed]
- Goverman, J. Autoimmune T Cell Responses in the Central Nervous System. Nat. Rev. Immunol. 2009, 9, 393–407. [Google Scholar] [CrossRef] [PubMed]
- Peeters, L.M.; Vanheusden, M.; Somers, V.; Van Wijmeersch, B.; Stinissen, P.; Broux, B.; Hellings, N. Cytotoxic CD4+ T Cells Drive Multiple Sclerosis Progression. Front. Immunol. 2017, 8, 1160. [Google Scholar] [CrossRef] [PubMed]
- Shao, S.; He, F.; Yang, Y.; Yuan, G.; Zhang, M.; Yu, X. Th17 Cells in Type 1 Diabetes. Cell. Immunol. 2012, 280, 16–21. [Google Scholar] [CrossRef] [PubMed]
- Ziegler, A.G.; Rewers, M.; Simell, O.; Simell, T.; Lempainen, J.; Steck, A.; Winkler, C.; Ilonen, J.; Veijola, R.; Knip, M.; et al. Seroconversion to Multiple Islet Autoantibodies and Risk of Progression to Diabetes in Children. JAMA 2013, 309, 2473–2479. [Google Scholar] [CrossRef] [PubMed]
- Serreze, D.V.; Chapman, H.D.; Varnum, D.S.; Hanson, M.S.; Reifsnyder, P.C.; Richard, S.D.; Fleming, S.A.; Leiter, E.H.; Shultz, L.D. B Lymphocytes Are Essential for the Initiation of T Cell-Mediated Autoimmune Diabetes: Analysis of a New "Speed Congenic" Stock of NOD. Igμ Null. Mice. J. Exp. Med. 1996, 184, 2049–2053. [Google Scholar] [CrossRef] [PubMed]
- van Belle, T.L.; Coppieters, K.T.; von Herrath, M.G. Type 1 Diabetes: Etiology, Immunology, and Therapeutic Strategies. Physiol. Rev. 2011, 91, 79–118. [Google Scholar] [CrossRef] [PubMed]
- Eizirik, D.L.; Colli, M.L.; Ortis, F. The Role of Inflammation in Insulitis and β-Cell Loss in Type 1 Diabetes. Nat. Rev. Endocrinol. 2009, 5, 219–226. [Google Scholar] [CrossRef] [PubMed]
- Mandrup-Poulsen, T. The Role of Interleukin-1 in the Pathogenesis of IDDM. Diabetologia 1996, 39, 1005–1029. [Google Scholar] [CrossRef] [PubMed]
- Cheng, J.; Yin, M.; Tang, X.; Yan, X.; Xie, Y.; He, B.; Li, X.; Zhou, Z. Residual β-Cell Function after 10 Years of Autoimmune Type 1 Diabetes: Prevalence, Possible Determinants, and Implications for Metabolism. Ann. Transl. Med. 2021, 9, 650. [Google Scholar] [CrossRef] [PubMed]
- Hansen de Almeida, M.; Rodrigues Dantas, J.; Barone, B.; Marcel Serfaty, F.; Kupfer, R.; Albernaz, M.; Rocio Bencke, M.; Zajdenverg, L.; Rodacki, M.; Egídio Paulo de Oliveira, J. Residual C-Peptide in Patients with Type 1 Diabetes and Multiethnic Backgrounds. Clinics 2013, 68, 123–126. [Google Scholar] [CrossRef] [PubMed]
- Baidal, D.A.; Ballou, C.M.; Rickels, M.R.; Berney, T.; Pattou, F.; Payne, E.H.; Barton, F.B.; Alejandro, R. CITR Investigators. Predictive Value of C-Peptide Measures for Clinical Outcomes of β-Cell Replacement Therapy in Type 1 Diabetes: Report from the Collaborative Islet Transplant Registry (CITR). Diabetes Care 2023, 46, 697–703. [Google Scholar] [CrossRef] [PubMed]
- Friedenstein, A.J.; Chailakhyan, R.K.; Latsinik, N.V.; Panasyuk, A.F.; Keiliss-Borok, I.V. Stromal Cells Responsible for Transferring the Microenvironment of the Hemopoietic Tissues. Cloning In Vitro and Retransplantation In Vivo. Transplantation 1974, 17, 331–340. [Google Scholar] [CrossRef] [PubMed]
- Dominici, M.; Le Blanc, K.; Mueller, I.; Slaper-Cortenbach, I.; Marini, F.; Krause, D.; Deans, R.; Keating, A.; Prockop, D.J.; Horwitz, E. Minimal Criteria for Defining Multipotent Mesenchymal Stromal Cells. The International Society for Cellular Therapy Position Statement. Cytotherapy 2006, 8, 315–317. [Google Scholar] [CrossRef] [PubMed]
- Kholodenko, I.V.; Kholodenko, R.V.; Yarygin, K.N. The Crosstalk between Mesenchymal Stromal/Stem Cells and Hepatocytes in Homeostasis and under Stress. Int. J. Mol. Sci. 2023, 24, 15212. [Google Scholar] [CrossRef] [PubMed]
- Kholodenko, I.V.; Yarygin, K.N. Hepatic Macrophages as Targets for the MSC-Based Cell Therapy in Non-Alcoholic Steatohepatitis. Biomedicines 2023, 11, 3056. [Google Scholar] [CrossRef] [PubMed]
- Yarygin, K.N.; Lupatov, A.Y.; Sukhikh, G.T. Modulation of Immune Responses by Mesenchymal Stromal Cells. Bull. Exp. Biol. Med. 2016, 161, 561–565. [Google Scholar] [CrossRef] [PubMed]
- Lupatov, A.Y.; Saryglar, R.Y.; Vtorushina, V.V.; Poltavtseva, R.A.; Bystrykh, O.A.; Chuprynin, V.D.; Krechetova, L.V.; Pavlovich, S.V.; Yarygin, K.N.; Sukhikh, G.T. Mesenchymal Stromal Cells Isolated from Ectopic but Not Eutopic Endometrium Display Pronounced Immunomodulatory Activity In Vitro. Biomedicines 2021, 9, 1286. [Google Scholar] [CrossRef] [PubMed]
- Duffy, M.M.; Ritter, T.; Ceredig, R.; Griffin, M.D. Mesenchymal Stem Cell Effects on T-Cell Effector Pathways. Stem Cell Res. Ther. 2011, 2, 34. [Google Scholar] [CrossRef] [PubMed]
- Abbasi, B.; Shamsasenjan, K.; Ahmadi, M.; Beheshti, S.A.; Saleh, M. Mesenchymal Stem Cells and Natural Killer Cells Interaction Mechanisms and Potential Clinical Applications. Stem Cell Res. Ther. 2022, 13, 97. [Google Scholar] [CrossRef] [PubMed]
- Luque-Campos, N.; Bustamante-Barrientos, F.A.; Pradenas, C.; García, C.; Araya, M.J.; Bohaud, C.; Contreras-López, R.; Elizondo-Vega, R.; Djouad, F.; Luz-Crawford, P.; Vega-Letter, A.M. The Macrophage Response Is Driven by Mesenchymal Stem Cell-Mediated Metabolic Reprogramming. Front. Immunol. 2021, 12, 624746. [Google Scholar] [CrossRef] [PubMed]
- Li, H.; Wang, T.; Yang, C.; Dong, W.; Wu, J.; Zhang, J.; Xu, F.; Xie, Z.; Liang, L.; Zhang, K.; et al. Mesenchymal Stem Cells Regulating Macrophage Polarization. Int. Immunopharmacol. 2026, 168, 115801. [Google Scholar] [CrossRef] [PubMed]
- Kholodenko, I.V.; Kholodenko, R.V.; Majouga, A.G.; Yarygin, K.N. Apoptotic MSCs and MSC-Derived Apoptotic Bodies as New Therapeutic Tools. Curr. Issues Mol. Biol. 2022, 44, 5153–5172. [Google Scholar] [CrossRef] [PubMed]
- Li, F.; Zhang, J.; Yi, K.; Wang, H.; Wei, H.; Chan, H.F.; Tao, Y.; Li, M. Delivery of Stem Cell Secretome for Therapeutic Applications. ACS Appl. Bio Mater. 2022, 5, 2009–2030. [Google Scholar] [CrossRef] [PubMed]
- Negrete-Diaz, F.; Martinez-Rodriguez, S.; Guedan-Duran, A.; Romero-Lopez, A.; Panetsos, F. MSC Secretomes as a Cell-Free Therapeutic Platform: Molecular Heterogeneity, Disease-Specific Bioactivity, Delivery Strategies, and Regulatory Translation across Six Major Disease Areas. Pharmacol. Res. 2026, 230, 108245. [Google Scholar] [CrossRef] [PubMed]
- Kavanagh, D.P.; Suresh, S.; Newsome, P.N.; Frampton, J.; Kalia, N. Pretreatment of Mesenchymal Stem Cells Manipulates Their Vasculoprotective Potential While Not Altering Their Homing Within the Injured Gut. Stem Cells 2015, 33, 2785–2797. [Google Scholar] [CrossRef] [PubMed]
- Su, Y.; Xu, C.; Cheng, W.; Zhao, Y.; Sui, L.; Zhao, Y. Pretreated Mesenchymal Stem Cells and Their Secretome: Enhanced Immunotherapeutic Strategies. Int. J. Mol. Sci. 2023, 24, 1277. [Google Scholar] [CrossRef] [PubMed]
- Song, Y.; Liang, F.; Tian, W.; Rayhill, E.; Ye, L.; Tian, X. Optimizing Therapeutic Outcomes: Preconditioning Strategies for MSC-Derived Extracellular Vesicles. Front. Pharmacol. 2025, 16, 1509418. [Google Scholar] [CrossRef] [PubMed]
- Schmelzer, E.; McKeel, D.T.; Gerlach, J.C. Characterization of Human Mesenchymal Stem Cells from Different Tissues and Their Membrane Encasement for Prospective Transplantation Therapies. BioMed Res. Int. 2019, 2019, 6376271. [Google Scholar] [CrossRef] [PubMed]
- Ventura, A.; Libonati, A.; Marcozzi, S.; Ucci, M.A.; Salvatore, G.; Galgani, A.; Pirrò, S.; Massimiani, M.; Picozza, M.; Russo, R.; et al. Comparative Analysis of Human Mesenchymal Stromal Cells from Adipose Tissue and Dental Pulp: Phenotypic Characterization and Secretome Profiling. Biol. Direct 2025, 20, 111. [Google Scholar] [CrossRef] [PubMed]
- Cao, C.; Maska, B.; Malik, M.A.; Tagett, R.; Kaigler, D. Immunomodulatory Differences between Mesenchymal Stem Cells from Different Oral Tissues. Heliyon 2023, 10, e23317. [Google Scholar] [CrossRef] [PubMed]
- Mattar, P.; Bieback, K. Comparing the Immunomodulatory Properties of Bone Marrow, Adipose Tissue, and Birth-Associated Tissue Mesenchymal Stromal Cells. Front. Immunol. 2015, 6, 560. [Google Scholar] [CrossRef] [PubMed]
- Wagner, W.; Wein, F.; Seckinger, A.; Frankhauser, M.; Wirkner, U.; Krause, U.; Blake, J.; Schwager, C.; Eckstein, V.; Ansorge, W.; Ho, A.D. Comparative Characteristics of Mesenchymal Stem Cells from Human Bone Marrow, Adipose Tissue, and Umbilical Cord Blood. Exp. Hematol. 2005, 33, 1402–1416. [Google Scholar] [CrossRef] [PubMed]
- Cho, K.A.; Park, M.; Kim, Y.H.; Woo, S.Y.; Ryu, K.H. RNA Sequencing Reveals a Transcriptomic Portrait of Human Mesenchymal Stem Cells from Bone Marrow, Adipose Tissue, and Palatine Tonsils. Sci. Rep. 2017, 7, 17114. [Google Scholar] [CrossRef] [PubMed]
- Lee, M.J.; Park, K.; Won, S.; Jo, C.H. Comparative Transcriptomic Profiling of Mesenchymal Stem Cells from Distinct Tissue Origins and Isolation Methods Highlights the Stability and Immunomodulatory Signature of Umbilical Cord-Derived Smumf Cells. Tissue Eng. Regen. Med. 2026, 23, 157–173. [Google Scholar] [CrossRef] [PubMed]
- Wu, C.; Jin, Z.P.; Weng, S.Q.; Zhu, J.M.; Dong, L. Stem Cell Therapy for Inflammatory Diseases: Progress, Challenges, and Future Directions. MedComm 2026, 7, e70616. [Google Scholar] [CrossRef] [PubMed]
- Liu, L.; Wong, C.W.; Han, M.; Farhoodi, H.P.; Liu, G.; Liu, Y.; Liao, W.; Zhao, W. Meta-Analysis of Preclinical Studies of Mesenchymal Stromal Cells to Treat Rheumatoid Arthritis. EBioMedicine 2019, 47, 563–577. [Google Scholar] [CrossRef] [PubMed]
- Chen, Y.; Gao, R.; Guo, X.; Wang, Y.; Zhang, Y.; Li, Z.; Liu, Y.; Wang, Y.; Zhou, Y.; Qin, L.; Zhang, Y. Mesenchymal Stromal Cell Therapy for Rheumatoid Arthritis: Long-Term Efficacy, Safety, and Mechanistic Insights. Rheumatol. Autoimmun. 2026, 6, 71–82. [Google Scholar] [CrossRef]
- Nahayati, M.A.; Ghavidel Yazdi, S.; Hassanisabzevar, M.; Baniasadi, P.; Forouzanfar, F.; Saburi, E. Mesenchymal Stem Cells in Clinical Trials for Multiple Sclerosis: A Systematic Literature Review and Review of Clinical Trials. Mult. Scler. Relat. Disord. 2025, 103, 106694. [Google Scholar] [CrossRef] [PubMed]
- Wong, R.Y. Role of Mesenchymal Stem-Cell-Based Therapy in Multiple Sclerosis: Insights from Recent Preclinical and Clinical Studies. Egypt. J. Neurol. Psychiatry Neurosurg. 2025, 61, 102. [Google Scholar] [CrossRef]
- Liu, J.; Wan, X.X.; Zheng, S.Y.; Khan, M.A.; He, H.H.; Feng, Y.X.; Xiao, J.G.; Chen, Y.; Hu, X.M.; Zhang, Q.; Xiong, K. Mesenchymal Stem Cell Transplantation in Type 1 Diabetes Treatment: Current Advances and Future Opportunity. Curr. Stem Cell Res. Ther. 2024, 19, 1175–1184. [Google Scholar] [CrossRef] [PubMed]
- Mou, L.; Wang, T.B.; Wang, X.; Pu, Z. Advancing Diabetes Treatment: The Role of Mesenchymal Stem Cells in Islet Transplantation. Front. Immunol. 2024, 15, 1389134. [Google Scholar] [CrossRef] [PubMed]
- Ghoneim, M.A.; Gabr, M.M.; El-Halawani, S.M.; Refaie, A.F. Current Status of Stem Cell Therapy for Type 1 Diabetes: A Critique and a Prospective Consideration. Stem Cell Res. Ther. 2024, 15, 23. [Google Scholar] [CrossRef] [PubMed]
- Wei, S.; Li, M.; Wang, Q.; Zhao, Y.; Du, F.; Chen, Y.; Deng, S.; Shen, J.; Wu, K.; Yang, J.; et al. Mesenchymal Stromal Cells: New Generation Treatment of Inflammatory Bowel Disease. J. Inflamm. Res. 2024, 17, 3307–3334. [Google Scholar] [CrossRef] [PubMed]
- Wang, P.-F.; Mu, S.-H.; Jin, F.; Sui, B.-D. Mesenchymal Stem Cell Therapy for Ulcerative Colitis: Opportunities and Challenges in Precision Medicine. Clin. Transl. Discov. 2025, 5, e70101. [Google Scholar] [CrossRef]
- Barra, J.M.; Tse, H.M. Redox-Dependent Inflammation in Islet Transplantation Rejection. Front. Endocrinol. 2018, 9, 175. [Google Scholar] [CrossRef] [PubMed]
- Langlois, A.; Pinget, M.; Kessler, L.; Bouzakri, K. Islet Transplantation: Current Limitations and Challenges for Successful Outcomes. Cells 2024, 13, 1783. [Google Scholar] [CrossRef] [PubMed]
- Rackham, C.L.; Dhadda, P.K.; Chagastelles, P.C.; Simpson, S.J.S.; Dattani, A.A.; Bowe, J.E.; Jones, P.M.; King, A.J.F. Pre-Culturing Islets with Mesenchymal Stromal Cells Using a Direct Contact Configuration Is Beneficial for Transplantation Outcome in Diabetic Mice. Cytotherapy 2013, 15, 449–459. [Google Scholar] [CrossRef] [PubMed]
- Kerby, A.; Jones, E.S.; Jones, P.M.; King, A.J. Co-Transplantation of Islets with Mesenchymal Stem Cells in Microcapsules Demonstrates Graft Outcome Can Be Improved in an Isolated-Graft Model of Islet Transplantation in Mice. Cytotherapy 2013, 15, 192–200. [Google Scholar] [CrossRef] [PubMed]
- Niknam, B.; Ayenehdeh, J.M.; Hossein-Khannazer, N.; Vosough, M.; Tajik, N. Adipose Tissue-Derived Mesenchymal Stromal Cells Modulate Inflammatory Response and Improve Allograft Islet Transplant in Mice Model of Type 1. Diabetes Endocr. Res. 2024, 49, 223–231. [Google Scholar] [CrossRef] [PubMed]
- Arzouni, A.A.; Vargas-Seymour, A.; Dhadda, P.K.; Rackham, C.L.; Huang, G.-C.; Choudhary, P.; King, A.J.F.; Jones, P.M. Characterization of the Effects of Mesenchymal Stromal Cells on Mouse and Human Islet Function. Stem Cells Transl. Med. 2019, 8, 935–944. [Google Scholar] [CrossRef] [PubMed]
- Hong, T.W.; Sullivan, R.; Arora, R.; Lonsane, A.; Lyu, Z.; Caxaria, S.; Huang, T.C.; Daniels Gatward, L.F.; Burgoyne, T.; King, A.J.F.; et al. Mesenchymal Stromal Cells Improve Islet β-Cell Functional Survival: Analysis of Extracellular Vesicle-Trafficked Proteins and miRNAs. Cells 2026, 15, 992. [Google Scholar] [CrossRef] [PubMed]
- World Health Organization. Classification of Diabetes Mellitus. Available online: https://apps.who.int/iris/handle/10665/325182 (accessed on 9 September 2026).
- Betz, A.L.; Gilboe, D.D.; Drewes, L.R. The Characteristics of Glucose Transport across the Blood Brain Barrier and Its Relation to Cerebral Glucose Metabolism. Adv. Exp. Med. Biol. 1976, 69, 133–149. [Google Scholar] [CrossRef] [PubMed]
- Honka, M.J.; Latva-Rasku, A.; Bucci, M.; Virtanen, K.A.; Hannukainen, J.C.; Kalliokoski, K.K.; Nuutila, P. Insulin-Stimulated Glucose Uptake in Skeletal Muscle, Adipose Tissue and Liver: A Positron Emission Tomography Study. Eur. J. Endocrinol. 2018, 178, 523–531. [Google Scholar] [CrossRef] [PubMed]
- Woerle, H.J.; Gerich, J. Glucose Physiology, Normal. Encycl. Endocr. Dis. 2004, 2, 263–270. [Google Scholar] [CrossRef]
- Nuschke, A.; Rodrigues, M.; Wells, A.W.; Sylakowski, K.; Wells, A. Mesenchymal Stem Cells/Multipotent Stromal Cells (MSCs) Are Glycolytic and Thus Glucose Is a Limiting Factor of In Vitro Models of MSC Starvation. Stem Cell Res. Ther. 2016, 7, 179. [Google Scholar] [CrossRef] [PubMed]
- Weil, B.R.; Abarbanell, A.M.; Herrmann, J.L.; Wang, Y.; Meldrum, D.R. High Glucose Concentration in Cell Culture Medium Does Not Acutely Affect Human Mesenchymal Stem Cell Growth Factor Production or Proliferation. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2009, 296, R1735–R1743. [Google Scholar] [CrossRef] [PubMed]
- Stolzing, A.; Coleman, N.; Scutt, A. Glucose-Induced Replicative Senescence in Mesenchymal Stem Cells. Rejuvenation Res. 2006, 9, 31–35. [Google Scholar] [CrossRef] [PubMed]
- Li, Y.-M.; Schilling, T.; Benisch, P.; Zeck, S.; Meissner-Weigl, J.; Schneider, D.; Limbert, C.; Seufert, J.; Kassem, M.; Schütze, N.; et al. Effects of High Glucose on Mesenchymal Stem Cell Proliferation and Differentiation. Biochem. Biophys. Res. Commun. 2007, 363, 209–215. [Google Scholar] [CrossRef] [PubMed]
- Chang, T.-C.; Hsu, M.-F.; Wu, K.K. High Glucose Induces Bone Marrow-Derived Mesenchymal Stem Cell Senescence by Upregulating Autophagy. PLoS ONE 2015, 10, e0126537. [Google Scholar] [CrossRef] [PubMed]
- Keats, E.; Khan, Z.A. Unique Responses of Stem Cell-Derived Vascular Endothelial and Mesenchymal Cells to High Levels of Glucose. PLoS ONE 2012, 7, e38752. [Google Scholar] [CrossRef] [PubMed]
- Hankamolsiri, W.; Manochantr, S.; Tantrawatpan, C.; Tantikanlayaporn, D.; Tapanadechopone, P.; Kheolamai, P. The Effects of High Glucose on Adipogenic and Osteogenic Differentiation of Gestational Tissue-Derived MSCs. Stem Cells Int. 2016, 2016, 9674614. [Google Scholar] [CrossRef] [PubMed]
- Liu, Y.; Li, Y.; Nan, L.-P.; Wang, F.; Zhou, S.-F.; Wang, J.-C.; Feng, X.-M.; Zhang, L. The Effect of High Glucose on the Biological Characteristics of Nucleus Pulposus-Derived Mesenchymal Stem Cells. Cell Biochem. Funct. 2020, 38, 130–140. [Google Scholar] [CrossRef] [PubMed]
- D'Esposito, V.; Lecce, M.; Marenzi, G.; Cabaro, S.; Ambrosio, M.R.; Sammartino, G.; Misso, S.; Migliaccio, T.; Liguoro, P.; Oriente, F.; et al. Platelet-Rich Plasma Counteracts Detrimental Effect of High-Glucose Concentrations on Mesenchymal Stem Cells from Bichat Fat Pad. J. Tissue Eng. Regen. Med. 2020, 14, 701–713. [Google Scholar] [CrossRef] [PubMed]
- Abu-El-Rub, E.; Almahasneh, F.; Khasawneh, R.R.; Alzu'bi, A.; Ghorab, D.; Almazari, R.; Magableh, H.; Sanajleh, A.; Shlool, H.; Mazari, M.; et al. Human Mesenchymal Stem Cells Exhibit Altered Mitochondrial Dynamics and Poor Survival in High Glucose Microenvironment. World J. Stem Cells 2023, 15, 1093–1103. [Google Scholar] [CrossRef] [PubMed]
- Deschepper, M.; Oudina, K.; David, B.; Myrtil, V.; Collet, C.; Bensidhoum, M.; Logeart-Avramoglou, D.; Petite, H. Survival and Function of Mesenchymal Stem Cells (MSCs) Depend on Glucose to Overcome Exposure to Long-Term, Severe and Continuous Hypoxia. J. Cell. Mol. Med. 2011, 15, 1505–1514. [Google Scholar] [CrossRef] [PubMed]
- Khasawneh, R.R.; Abu-El-Rub, E.; Almahasneh, F.A.; Alzu'bi, A.; Zegallai, H.M.; Almazari, R.A.; Magableh, H.; Mazari, M.H.; Shlool, H.F.; Sanajleh, A.K. Addressing the Impact of High Glucose Microenvironment on the Immunosuppressive Characteristics of Human Mesenchymal Stem Cells. IUBMB Life 2024, 76, 286–295. [Google Scholar] [CrossRef] [PubMed]
- Saki, N.; Jalalifar, M.A.; Soleimani, M.; Hajizamani, S.; Rahim, F. Adverse Effect of High Glucose Concentration on Stem Cell Therapy. Int. J. Hematol. Oncol. Stem Cell Res. 2013, 7, 34–40. [Google Scholar] [PubMed]
- Aikawa, E.; Fujita, R.; Asai, M.; Kaneda, Y.; Tamai, K. Receptor for Advanced Glycation End Products-Mediated Signaling Impairs the Maintenance of Bone Marrow Mesenchymal Stromal Cells in Diabetic Model Mice. Stem Cells Dev. 2016, 25, 1721–1732. [Google Scholar] [CrossRef] [PubMed]
- Kornicka, K.; Houston, J.; Marycz, K. Dysfunction of Mesenchymal Stem Cells Isolated from Metabolic Syndrome and Type 2 Diabetic Patients as Result of Oxidative Stress and Autophagy May Limit Their Potential Therapeutic Use. Stem Cell Rev. Rep. 2018, 14, 337–345. [Google Scholar] [CrossRef] [PubMed]
- Berezin, A. Metabolic Memory Phenomenon in Diabetes Mellitus: Achievements and Perspectives. Diabetes Metab. Syndr. 2016, 10, S176–S183. [Google Scholar] [CrossRef] [PubMed]
- Grohová, A.; Dánˇová, K.; Špíšek, R.; Palová-Jelínková, L. Cell Based Therapy for Type 1 Diabetes: Should We Take Hyperglycemia into Account? Front Immunol. 2019, 10, 79. [Google Scholar] [CrossRef] [PubMed]
- Mahmoud, M.; Abu-Shahba, N.; Azmy, O.; El-Badri, N. Impact of Diabetes Mellitus on Human Mesenchymal Stromal Cell Biology and Functionality: Implications for Autologous Transplantation. Stem Cell Rev. Rep. 2019, 15, 194–217. [Google Scholar] [CrossRef] [PubMed]
- Tan, S.; Wu, W.; Chen, Y.; Gao, H. High Glucose Induces Senescence in Synovial Mesenchymal Stem Cells through Mitochondrial Dysfunction. BMC Oral Health 2025, 25, 569. [Google Scholar] [CrossRef] [PubMed]
- Pearson, J.A.; Wong, F.S.; Wen, L. The Importance of the Non Obese Diabetic (NOD) Mouse Model in Autoimmune Diabetes. J. Autoimmun. 2016, 66, 76–88. [Google Scholar] [CrossRef] [PubMed]
- Radenković, M.; Stojanović, M.; Prostran, M. Experimental Diabetes Induced by Alloxan and Streptozotocin: The Current State of the Art. J. Pharmacol. Toxicol. Methods 2016, 78, 13–31. [Google Scholar] [CrossRef] [PubMed]
- Mikłosz, A.; Chabowski, A. Adipose-Derived Mesenchymal Stem Cells Therapy as a New Treatment Option for Diabetes Mellitus. J. Clin. Endocrinol. Metab. 2023, 108, 1889–1897. [Google Scholar] [CrossRef] [PubMed]
- Gao, J.; Li, B.; Tian, H.; Li, C.; Merzlikin, N.; Han, D.; Ling, Z.; Zhang, Z.; Zhu, W.; Dai, J.; et al. SPARC-Modified Mesenchymal Stem Cells Promote Recovery of β-Cells and Insulin Secretion by Calcium Ion Homeostasis. Stem Cell Res. Ther. 2025, 16, 607. [Google Scholar] [CrossRef] [PubMed]
- Harries, L.W.; McCulloch, L.J.; Holley, J.E.; Rawling, T.J.; Welters, H.J.; Kos, K. A Role for SPARC in the Moderation of Human Insulin Secretion. PLoS ONE 2013, 8, e68253. [Google Scholar] [CrossRef] [PubMed]
- Atorrasagasti, C.; Onorato, A.; Gimeno, M.L.; Andreone, L.; Garcia, M.; Malvicini, M.; Fiore, E.; Bayo, J.; Perone, M.J.; Mazzolini, G.D. SPARC Is Required for the Maintenance of Glucose Homeostasis and Insulin Secretion in Mice. Clin. Sci. 2019, 133, 351–365. [Google Scholar] [CrossRef] [PubMed]
- Khalil, D.Y.; Hussein, R.H.; El-Kholy, W.M. Mesenchymal Stem Cell-Derived Exosomes Loaded with Selenium or Nano Selenium as a Novel Therapeutic Paradigm for Streptozotocin-Induced Type 1 Diabetes in Rats. Biology 2024, 13, 253. [Google Scholar] [CrossRef]
- Sabry, D.; Marzouk, S.; Zakaria, R.; Ibrahim, H.A.; Samir, M. The Effect of Exosomes Derived from Mesenchymal Stem Cells in the Treatment of Induced Type 1 Diabetes Mellitus in Rats. Biotechnol. Lett. 2020, 42, 1597–1610. [Google Scholar] [CrossRef] [PubMed]
- Nojehdehi, S.; Soudi, S.; Hesampour, A.; Rasouli, S.; Soleimani, M.; Hashemi, S.M. Immunomodulatory Effects of Mesenchymal Stem Cell-Derived Exosomes on Experimental Type-1 Autoimmune Diabetes. J. Cell. Biochem. 2018, 119, 9433–9443. [Google Scholar] [CrossRef] [PubMed]
- Sun, Y.; Tao, Q.; Wu, X.; Zhang, L.; Liu, Q.; Wang, L. The Utility of Exosomes in Diagnosis and Therapy of Diabetes Mellitus and Associated Complications. Front. Endocrinol. 2021, 12, 756581. [Google Scholar] [CrossRef] [PubMed]
- Sun, Y.L.; Shang, L.R.; Liu, R.H.; Li, X.Y.; Zhang, S.H.; Ren, Y.K.; Fu, K.; Cheng, H.B.; Yahaya, B.H.; Liu, Y.L.; Lin, J.T. Therapeutic Effects of Menstrual Blood-Derived Endometrial Stem Cells on Mouse Models of Streptozotocin-Induced Type 1 Diabetes. World J. Stem Cells 2022, 14, 104–116. [Google Scholar] [CrossRef] [PubMed]
- Jurewicz, M.; Yang, S.; Augello, A.; Godwin, J.G.; Moore, R.F.; Azzi, J.; Fiorina, P.; Atkinson, M.; Sayegh, M.H.; Abdi, R. Congenic Mesenchymal Stem Cell Therapy Reverses Hyperglycemia in Experimental Type 1 Diabetes. Diabetes 2010, 59, 3139–3147. [Google Scholar] [CrossRef] [PubMed]
- Khatri, R.; Petry, S.F.; Linn, T. Intrapancreatic MSC Transplantation Facilitates Pancreatic Islet Regeneration. Stem Cell Res. Ther. 2021, 12, 121. [Google Scholar] [CrossRef] [PubMed]
- Li, L.; Hui, H.; Jia, X.; Zhang, J.; Liu, Y.; Xu, Q.; Zhu, D. Infusion with Human Bone Marrow-Derived Mesenchymal Stem Cells Improves β-Cell Function in Patients and Non-Obese Mice with Severe Diabetes. Sci. Rep. 2016, 6, 37894. [Google Scholar] [CrossRef] [PubMed]
- Refaie, A.F.; Elbassiouny, B.L.; Kloc, M.; Sabek, O.M.; Khater, S.M.; Ismail, A.M.; Mohamed, R.H.; Ghoneim, M.A. From Mesenchymal Stromal/Stem Cells to Insulin-Producing Cells: Immunological Considerations. Front. Immunol. 2021, 12, 690623. [Google Scholar] [CrossRef] [PubMed]
- Piekarska, K.; Urban-Wójciuk, Z.; Kurkowiak, M.; Pelikant-Małecka, I.; Schumacher, A.; Sakowska, J.; Spodnik, J.H.; Arcimowicz, Ł.; Zielińska, H.; Tymoniuk, B.; et al. Mesenchymal Stem Cells Transfer Mitochondria to Allogeneic Tregs in an HLA-Dependent Manner Improving Their Immunosuppressive Activity. Nat. Commun. 2022, 13, 856. [Google Scholar] [CrossRef] [PubMed]
- Zhang, W.; Ling, Q.; Wang, B.; Wang, K.; Pang, J.; Lu, J.; Bi, Y.; Zhu, D. Comparison of Therapeutic Effects of Mesenchymal Stem Cells from Umbilical Cord and Bone Marrow in the Treatment of Type 1 Diabetes. Stem Cell Res. Ther. 2022, 13, 406. [Google Scholar] [CrossRef] [PubMed]
- Isildar, B.; Ozkan, S.; Ercin, M.; Gezginci-Oktayoglu, S.; Oncul, M.; Koyuturk, M. 2D and 3D Cultured Human Umbilical Cord-Derived Mesenchymal Stem Cell-Conditioned Medium Has a Dual Effect in Type 1 Diabetes Model in Rats: Immunomodulation and Beta-Cell Regeneration. Inflamm. Regen. 2022, 42, 55. [Google Scholar] [CrossRef] [PubMed]
- Wu, C.; Liu, W.; Liu, Y.; Xu, T.; Li, M.; Li, X.; Wang, Y.; Meng, G.; Li, L.; Zheng, R.; Zhang, Y. Human Umbilical Cord Mesenchymal Stem Cell-Derived TGFBI Attenuates Streptozotocin-Induced Type 1 Diabetes Mellitus by Inhibiting T-Cell Proliferation. Hum. Cell 2023, 36, 997–1010. [Google Scholar] [CrossRef] [PubMed]
- Han, B.; Qi, S.; Hu, B.; Luo, H.; Wu, J. TGF-βi Promotes Islet Beta-Cell Function and Regeneration. J. Investig. Med. 2011, 59, 5833–5844. [Google Scholar] [CrossRef] [PubMed]
- Patry, M.; Teinturier, R.; Goehrig, D.; Zetu, C.; Ripoche, D.; Kim, I.S.; Bertolino, P.; Hennino, A. βig-h3 Represses T-Cell Activation in Type 1 Diabetes. Diabetes 2015, 64, 4212–4219. [Google Scholar] [CrossRef] [PubMed]
- Du, F.Y.; Zhou, F.; Zhao, N.; Bao, L.; Hu, C.B.; Lei, J.; Liu, A.Q.; Gao, Y.F.; Bao, L.H.; Ni, H.; et al. YAP1 Mediates the Dimensional and Chemical Coordination of Immunoregulation and Therapy in Extensively Passaged Mesenchymal Stem Cells. Theranostics 2025, 15, 1930–1948. [Google Scholar] [CrossRef] [PubMed]
- Lachaud, C.C.; Cobo-Vuilleumier, N.; Fuente-Martin, E.; Diaz, I.; Andreu, E.; Cahuana, G.M.; Tejedo, J.R.; Hmadcha, A.; Gauthier, B.R.; Soria, B. Umbilical Cord Mesenchymal Stromal Cells Transplantation Delays the Onset of Hyperglycemia in the RIP-B7.1 Mouse Model of Experimental Autoimmune Diabetes through Multiple Immunosuppressive and Anti-Inflammatory Responses. Front. Cell Dev. Biol. 2023, 11, 1089817. [Google Scholar] [CrossRef] [PubMed]
- Rajasalu, T.; Brosi, H.; Schuster, C.; Spyrantis, A.; Boehm, B.O.; Chen, L.; Reimann, J.; Schirmbeck, R. Deficiency in B7-H1 (PD-L1)/PD-1 Coinhibition Triggers Pancreatic Beta-Cell Destruction by Insulin-Specific, Murine CD8 T-Cells. Diabetes 2010, 59, 1966–1973. [Google Scholar] [CrossRef] [PubMed]
- Li, X.; Liu, J.; Xing, Z.; Tang, J.; Sun, H.; Zhang, X.; Lv, S.; Chen, Z.; Shi, M.; Chen, M.; et al. Polymorphonuclear Myeloid-Derived Suppressor Cells Link Inflammation and Damage Response after Trauma. J. Leukoc. Biol. 2021, 110, 1143–1161. [Google Scholar] [CrossRef] [PubMed]
- Rath, M.; Muller, I.; Kropf, P.; Closs, E.I.; Munder, M. Metabolism via Arginase or Nitric Oxide Synthase: Two Competing Arginine Pathways in Macrophages. Front. Immunol. 2014, 5, 532. [Google Scholar] [CrossRef] [PubMed]
- Nagaraj, S.; Collazo, M.; Corzo, C.A.; Youn, J.I.; Ortiz, M.; Quiceno, D.; Gabrilovich, D.I. Regulatory Myeloid Suppressor Cells in Health and Disease. Cancer Res. 2009, 69, 7503–7506. [Google Scholar] [CrossRef] [PubMed]
- Nagy, G.; Szekely, T.E.; Somogyi, A.; Herold, M.; Herold, Z. New Therapeutic Approaches for Type 1 Diabetes: Disease-Modifying Therapies. World J. Diabetes 2022, 13, 835–850. [Google Scholar] [CrossRef] [PubMed]
- Mićanović, D.; Stanisavljević, S.; Li, H.; Koprivica, I.; Jonić, N.; Stojanović, I.; Savković, V.; Saksida, T. Mesenchymal Stem Cells from Mouse Hair Follicles Inhibit the Development of Type 1 Diabetes. Int. J. Mol. Sci. 2024, 25, 5974. [Google Scholar] [CrossRef] [PubMed]
- Soleymani-Goloujeh, M.; Babaahmadi, M.; Shekari, F.; Barati, M.; Fallah, N.; Choshali, M.A.; Gholipour, N.M.; Hezavehei, M.; Azimi, M.; Yakhkeshi, S.; et al. Extracellular Vesicles Derived from Clonal Mesenchymal Stromal Cells Preconditioned by Indirect Hypoxia Modulate Immune Responses in Diabetic Mice More Effectively than Directly Preconditioned Vesicles. Stem Cell Res. Ther. 2025, 16, 458. [Google Scholar] [CrossRef] [PubMed]
- Hoseini, S.M.; Moghimi, F.; Hosseini, E.S.; Miresmaeili, S.M.; Mehrjardi, M.Y.V.; Dehghani, M.; Sheikhha, M.H.; Montazeri, F. Microenvironment-Dependent MSC Immunoregulation in Type 1 Diabetes: Insights from IFNγ Preconditioning. Genes Cells 2025, 30, e70032. [Google Scholar] [CrossRef] [PubMed]
- Liu, L.; Zheng, C.X.; Zhao, N.; Zhu, T.; Hu, C.B.; Zhang, N.; Chen, J.; Zhang, K.C.; Zhang, S.; Liu, J.X.; et al. Mesenchymal Stem Cell Aggregation-Released Extracellular Vesicles Induce CD31+ EMCN+ Vessels in Skin Regeneration and Improve Diabetic Wound Healing. Adv. Healthc. Mater. 2023, 12, e2300019. [Google Scholar] [CrossRef] [PubMed]
- Niu, L.; Ou, Q.; Ren, Q.; Li, Z.; Chen, H.; Lei, F.; Mao, X.; Shi, S.; Chen, Z.; Teng, W. Engineered Foxp1(high) Exosomes Ameliorates Systemic Lupus Erythematosus. Adv. Sci. 2025, 12, e15712. [Google Scholar] [CrossRef] [PubMed]
- Ren, Q.; Ou, Q.; Li, Z.; Niu, L.; Tang, D.; Liu, X.; Mao, X.; Shi, S. Extracellular Vesicles Inherit Lactate from Aggregated MSCs to Alleviate Type 1 Diabetes Mellitus via H2S-Induced CD8+ T Cell Exhaustion. J. Nanobiotechnology 2026, 24, 566. [Google Scholar] [CrossRef] [PubMed]
- U.S. National Library of Medicine. ClinicalTrials.gov. Available online: https://clinicaltrials.gov/ (accessed on 12 August 2026).
- Cai, J.; Wu, Z.; Xu, X.; Liao, L.; Chen, J.; Huang, L.; Wu, W.; Luo, F.; Wu, C.; Pugliese, A.; et al. Umbilical Cord Mesenchymal Stromal Cell with Autologous Bone Marrow Cell Transplantation in Established Type 1 Diabetes: A Pilot Randomized Controlled Open-Label Clinical Study to Assess Safety and Impact on Insulin Secretion. Diabetes Care 2016, 39, 149–157. [Google Scholar] [CrossRef]
- Wu, Z.; Xu, X.; Cai, J.; Chen, J.; Huang, L.; Wu, W.; Pugliese, A.; Li, S.; Ricordi, C.; Tan, J. Prevention of chronic diabetic complications in type 1 diabetes by co-transplantation of umbilical cord mesenchymal stromal cells and autologous bone marrow: a pilot randomized controlled open-label clinical study with 8-year follow-up. Cytotherapy 2022, 24, 421–427. [Google Scholar] [CrossRef]
- Carlsson, P.; Espes, D.; Sisay, S.; Davie, L.; Smith, C.; Svahn, M. Umbilical cord-derived mesenchymal stromal cells preserve endogenous insulin production in type 1 diabetes: a Phase I/II randomised double-blind placebo-controlled trial. Diabetologia 2023, 66, 1431–1441. [Google Scholar] [CrossRef]
- Seven-year follow-up data from ProTrans-Repeat demonstrate sustained disease-modifying effects of ProTrans in type 1 diabetes. Available online: https://www.nextcellpharma.com/press-releases/seven-year-follow-up-data-from-protrans-repeat-demonstrate-sustained-disease-modifying-effects-of-protrans-in-type-1-diabetes (accessed on 12 September 2026).
- Baan, C.; Dahlke, M.; Hoogduijn, M. Mesenchymal stem cells are short-lived and do not migrate beyond the lungs after intravenous infusion. Front. Immun. 2012, 3, e297. [Google Scholar] [CrossRef] [PubMed]
- Brownlee, M. The Pathobiology of Diabetic Complications: A Unifying Mechanism. Diabetes 2005, 54, 1615–1625. [Google Scholar] [CrossRef] [PubMed]
- Nathan, D.M.; Cleary, P.A.; Backlund, J.Y.; Genuth, S.M.; Lachin, J.M.; Orchard, T.J.; Raskin, P.; Zinman, B. Diabetes Control and Complications Trial/Epidemiology of Diabetes Interventions and Complications (DCCT/EDIC) Study Research Group. Intensive Diabetes Treatment and Cardiovascular Disease in Patients with Type 1 Diabetes. N. Engl. J. Med. 2005, 353, 2643–2653. [Google Scholar] [CrossRef] [PubMed]
- Baekkeskov, S.; Aanstoot, H.J.; Christgau, S.; Reetz, A.; Solimena, M.; Cascalho, M.; Folli, F.; Richter-Olesen, H.; De Camilli, P. Identification of the 64K Autoantigen in Insulin-Dependent Diabetes as the GABA-Synthesizing Enzyme Glutamic Acid Decarboxylase. Nature 1990, 347, 151–156. [Google Scholar] [CrossRef] [PubMed]
- Solimena, M.; Folli, F.; Denis-Donini, S.; Comi, G.C.; Pozza, G.; De Camilli, P.; Vicari, A.M. Autoantibodies to Glutamic Acid Decarboxylase in a Patient with Stiff-Man Syndrome, Epilepsy, and Type I Diabetes Mellitus. N. Engl. J. Med. 1988, 318, 1012–1020. [Google Scholar] [CrossRef] [PubMed]
- Erlander, M.G.; Tillakaratne, N.J.; Feldblum, S.; Patel, N.; Tobin, A.J. Two Genes Encode Distinct Glutamate Decarboxylases. Neuron 1991, 7, 91–100. [Google Scholar] [CrossRef] [PubMed]
- Feldman, E.L.; Callaghan, B.C.; Pop-Busui, R.; Zochodne, D.W.; Wright, D.E.; Bennett, D.L.; Bril, V.; Russell, J.W.; Viswanathan, V. Diabetic Neuropathy. Nat. Rev. Dis. Primers 2019, 5, 42. [Google Scholar] [CrossRef] [PubMed]
- Sun, J.; Sun, S.; Sun, Z.; Huang, Q.; Luo, L. Case Report: Thymoma-Associated GAD65 Autoimmunity: A Unifying Mechanism for Multi-Organ Injury Involving Nervous, Endocrine, and Renal Systems. Front. Immunol. 2026, 17, 1790631. [Google Scholar] [CrossRef] [PubMed]
- Vanderlugt, C.L.; Miller, S.D. Epitope Spreading in Immune-Mediated Diseases: Implications for Immunotherapy. Nat. Rev. Immunol. 2002, 2, 85–95. [Google Scholar] [CrossRef] [PubMed]
- Kandinov, I.; Knyazeva, A.; Lander, E.; Gryadunov, D.; Savvateeva, E. Molecular Portrait of Autoantigens in Type 1 Diabetes. Biomolecules 2025, 15, 1723. [Google Scholar] [CrossRef] [PubMed]
- Hu, C.; Sun, S.; Li, D.; Yu, L.; Guo, C.; Liu, S. Immunoproteomic Mediators of Diabetic Peripheral Neuropathy: Causal Insights from Mendelian Randomization and Single-Cell Validation. Front. Immunol. 2026, 17, 1681223. [Google Scholar] [CrossRef] [PubMed]
- Tuttle, K.R.; Bakris, G.L.; Bilous, R.W.; Chiang, J.L.; de Boer, I.H.; Goldstein-Fuchs, J.; Hirsch, I.B.; Kalantar-Zadeh, K.; Narva, A.S.; Navaneethan, S.D.; et al. Diabetic Kidney Disease: A Report from an ADA Consensus Conference. Diabetes Care 2014, 37, 2864–2883. [Google Scholar] [CrossRef] [PubMed]
- Tang, P.M.; Nikolic-Paterson, D.J.; Lan, H.Y. Macrophages: Versatile Players in Renal Inflammation and Fibrosis. Nat. Rev. Nephrol. 2019, 15, 144–158. [Google Scholar] [CrossRef] [PubMed]
- Campbell, R.C.; Ruggenenti, P.; Remuzzi, G. Proteinuria in Diabetic Nephropathy: Treatment and Evolution. Curr. Diabetes Rep. 2003, 3, 497–504. [Google Scholar] [CrossRef] [PubMed]
- Antonetti, D.A.; Barber, A.J.; Bronson, S.K.; Freeman, W.M.; Gardner, T.W.; Jefferson, L.S.; Kester, M.; Kimball, S.R.; Krady, J.K.; LaNoue, K.F.; et al. Diabetic Retinopathy: Seeing beyond Glucose-Induced Microvascular Disease. Diabetes 2006, 55, 2401–2411. [Google Scholar] [CrossRef] [PubMed]
- Ribak, C.E.; Vaughn, J.E.; Saito, K.; Barber, R.; Roberts, E. Immunocytochemical Localization of Glutamate Decarboxylase in Rat Substantia Nigra. Brain Res. 1976, 116, 287–298. [Google Scholar] [CrossRef] [PubMed]
- Kern, T.S. Contributions of Inflammatory Processes to the Development of the Early Stages of Diabetic Retinopathy. Exp. Diabetes Res. 2007, 2007, 95103. [Google Scholar] [CrossRef] [PubMed]
- Caplan, A.I. Mesenchymal Stem Cells in Regenerative Medicine. In Handbook of Stem Cells; Elsevier: Amsterdam, The Netherlands, 2013; pp. 493–502. [Google Scholar] [CrossRef]
- Uccelli, A.; Moretta, L.; Pistoia, V. Mesenchymal Stem Cells in Health and Disease. Nat. Rev. Immunol. 2008, 8, 726–736. [Google Scholar] [CrossRef] [PubMed]
- Li, Y.; Yue, G.; Yu, S.; Cheng, X.; Cao, Y.; Wang, X. Evaluating the Efficacy of Mesenchymal Stem Cells for Diabetic Neuropathy: A Systematic Review and Meta-Analysis of Preclinical Studies. Front. Bioeng. Biotechnol. 2024, 12, 1349050. [Google Scholar] [CrossRef] [PubMed]
- Zhu, Y.; Luo, M.; Bai, X.; Lou, Y.; Nie, P.; Jiang, S.; Li, J.; Li, B.; Luo, P. Administration of Mesenchymal Stem Cells in Diabetic Kidney Disease: Mechanisms, Signaling Pathways, and Preclinical Evidence. Mol. Cell. Biochem. 2022, 477, 2073–2092. [Google Scholar] [CrossRef] [PubMed]
- Cui, C.; Zang, N.; Song, J.; Guo, X.; He, Q.; Hu, H.; Yang, M.; Wang, Y.; Yang, J.; Zou, Y.; et al. Exosomes Derived from Mesenchymal Stem Cells Attenuate Diabetic Kidney Disease by Inhibiting Cell Apoptosis and Epithelial-to-Mesenchymal Transition via miR-424-5p. FASEB J. 2022, 36, e22517. [Google Scholar] [CrossRef] [PubMed]
- Sun, F.; Sun, Y.; Zhu, J.; Wang, X.; Ji, C.; Zhang, J.; Chen, S.; Yu, Y.; Xu, W.; Qian, H. Mesenchymal Stem Cells-Derived Small Extracellular Vesicles Alleviate Diabetic Retinopathy by Delivering NEDD4. Stem Cell Res. Ther. 2022, 13, 293. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Key Immunological Mechanisms in the Pathogenesis of T1D. Environmental trigger factors can initiate inflammation in the pancreas. Against a background of genetic predisposition, adaptive immune mechanisms become engaged in the inflammatory process. (1) DCs matured within a proinflammatory microenvironment can process fragments of β-cells killed by either exogenous triggers or autoimmune attack, and present their epitopes to naïve Th0 cells. Depending on the cytokines secreted by DCs, Th0 cells may differentiate into Th1 or Th17 subsets. Th1 cells promote CTL-mediated specific cytotoxicity against β-cells, whereas Th17 cells can recruit and activate neutrophils, which non-specifically destroy islet tissue through the release of reactive oxygen species (ROS). (2) Activated through CD40-dependent interaction with Th1 cells, DCs acquire the capacity to present autoantigen epitopes in the context of HLA-I to naïve CTLs (cross-presentation), which in turn differentiate into effector CTLs and gain the ability to destroy β-cells. (3) Under the influence of IFN-γ secreted by activated Th1 and NK cells, β-cells acquire HLA-II expression, which is absent under normal conditions. Concurrently, HLA-I expression is upregulated. Together, these effects enhance the adaptive immune response to autoantigens. (4) M1 macrophages secrete proinflammatory cytokines that can directly activate iNOS and trigger caspases in β-cells, inducing their apoptosis. Moreover, these cytokines—most notably IL-6—sustain chronic inflammation, promote effector T-cell proliferation, and suppress Tregs. (5) Under inflammatory conditions, post-translational modification of certain proteins in β-cells may become dysregulated. The resulting neoepitopes can be presented by DCs to lymphocytes that had previously passed central tolerance selection. Neoepitope-specific effector CTLs can then recognize and eliminate β-cells presenting these targets.
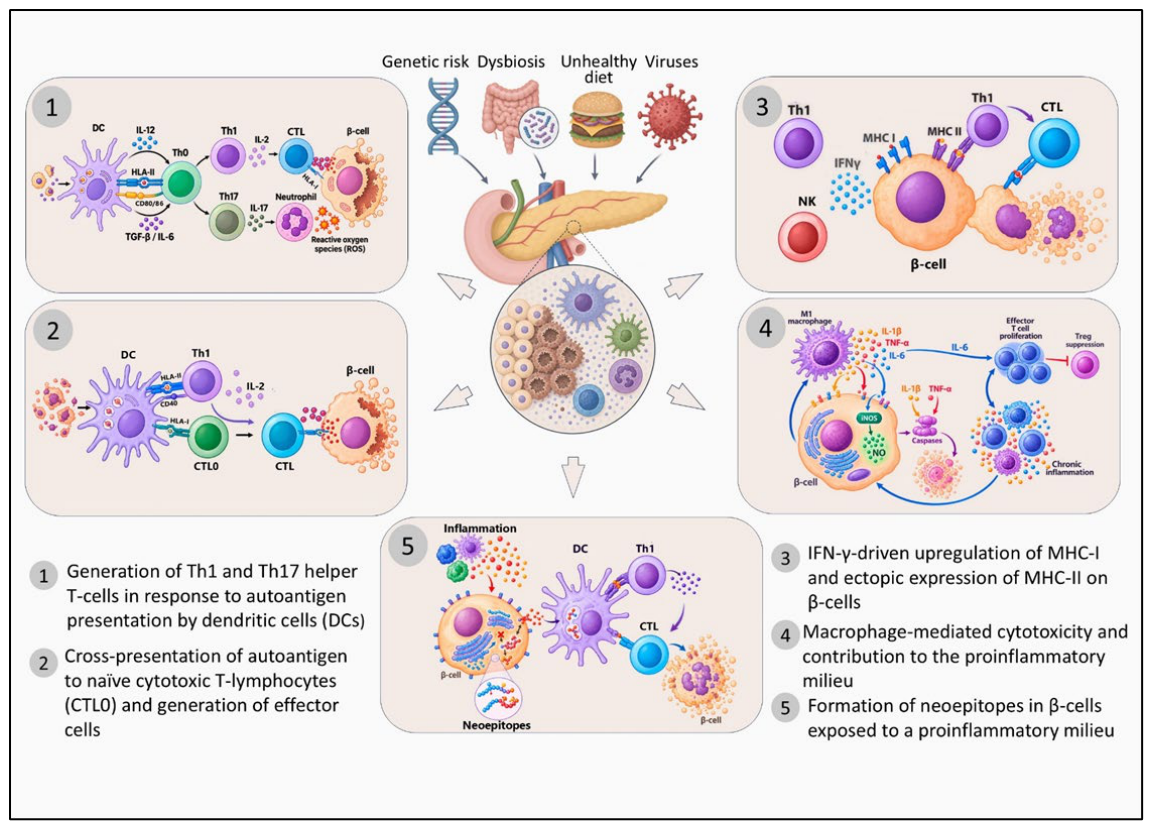

Table 1.
Molecular Mechanisms of MSC-Mediated Immunomodulation in T1D.
| Targets of MSCs | Molecular mediators | Immunomodulatory effect | Expected immunopathogenic shift |
|---|---|---|---|
| CD4⁺ T cells / Th1 | IDO1, PGE2, TGF-β, IL-10, HGF, PD-L1/PD-1 | ↓Th1 proliferation and activation; ↓ IFN-γ and other pro-inflammatory signals |
Decreased Th1-mediated autoantigen-specific responses and reduced inflammation |
| Naïve CD4⁺ T cells | TGF-β, PGE2, IDO1, cell–cell contact | ↑ generation and expansion of Treg cells | Restoration of peripheral immune tolerance |
| Th17 cells | PGE2/EP4, IDO1, TGF-β, IL-10, HGF | ↓ Th17 differentiation and proliferation | Attenuation of inflammation |
| Treg cells | TGF-β, IL-10, PGE2, HGF, cell–cell contact | ↑ Treg frequency and suppressive activity | Restoration of peripheral immune tolerance |
| CD8⁺ cytotoxic T cells (CTLs) | IDO1, PGE2, TGF-β, PD-L1/PD-1, HLA-G | ↓ proliferation and cytotoxicity | Attenuation of CTL-mediated β-cell destruction |
| B cells | IDO1, PGE2, PD-L1/PD-1, TGF-β, HGF, BAFF/APRIL | ↓ B-cell activation and proliferation; ↓ B-cell and plasma-cell survival; ↓ immunoglobulin production; ↓ autoantigen presentation by B-cells |
Suppressed autoantibody secretion |
| NK cells | IDO1, PGE2, HLA-G | ↓ NK-cell proliferation, activation, cytotoxicity; ↓ IFN-γ |
Attenuation of inflammation, decreased NK-cell cytotoxicity against β-cells |
| Dendritic cells (DCs) | IL-6, IL-10, PGE2, TGF-β, IDO1 | ↓ DCs differentiation from monocytes and HSC; ↓ DCs maturation; ↓ MHC-II/CD80/CD86; ↓ IL-12 |
Reduced presentation of β-cell autoantigens |
| Macrophages | PGE2, IL-10, TGF-β, TSG-6, IL-1Ra, HO-1 | M1 → M2 polarization; ↓ TNF-α, IL-1β, IL-6, and ROS; |
Attenuation of islet inflammation and direct β-cell destruction. |
| Neutrophils | HO-1, PGE2, TGF-β, and other paracrine factors | ↓ inflammatory activation; ↓ ROS; ↓ NETosis |
Suppression of inflammation and direct β-cell damage |
| β-cells | HGF, TGF-β, IL-10, VEGF, TSG-6, HO-1, EVs | ↓ β-cell apoptosis; ↓ inflammatory damage |
Preservation of β-cell function and islet regeneration |
Abbreviations: HO-1– heme oxygenase-1; IDO1 – indoleamine 2,3-dioxygenase 1; EVs – extracellular vesicles; PGE2 – Prostaglandin E2; ROS – Reactive Oxygen Species.
Table 2.
Clinical Trials of MSC-Based Immunomodulatory Therapy in T1D.
| Clinical trial | Phase | Patients (n; age) |
MSC | Route; Dose (x10⁶) | Follow-up (months) |
Main outcomes | Reported findings | |
|---|---|---|---|---|---|---|---|---|
|
NCT04078308 |
I/II |
n = 20; 8–40 |
Autologous BM-MSCs |
i.v. (×2); 1/kg |
12 |
Safety; insulin; C-peptide; autoantibodies; cytokines |
NR |
|
| NCT03920397 | II | n = 7; 16-35 |
Allogeneic AD-MSCs vitamin D | i.v.; 1/kg |
6 |
Safety; insulin; C-peptide; HbA1c; Treg | ↑C-peptide (40%); ↓ HbA1c |
|
| NCT04061746 | I/II | n = NR; 18–40 | Allogeneic UC-MSCs | i.v.; 2.5/kg; |
12 | Safety; C-peptide; insulin; immune markers | NR | |
| NCT03484741 | I/II | n = 15; 18–45 |
Autologous BM-MSCs + allogeneic UC-MSCs | i.v.; NR |
6 | Safety; insulin; C-peptide; HbA1c | NR | |
| NCT00690066 | II | n = NR; 12–35 |
Allogeneic BM-MSCs (PROCHYMAL®) | i.v. (multiple); NR |
24 | Insulin; C-peptide; HbA1c; GAD/IA-2 autoantibodies | NR | |
| NCT02763423 | II | n = 28; 12–35 |
Allogeneic UC-MSCs | i.v.; NR |
24 | Insulin; C-peptide; HbA1c; autoantibodies | ↑C-peptide (30%) ↓ exogenous insulin ↓ HbA1c |
|
| NCT01068951 | I/II | n = 20; 18–40 |
Autologous MSCs | i.v.; 2/kg |
12 | Safety; C-peptide | C-peptide preservation or increase compared with decline in controls | |
| NCT02893306 | II | n = 10; ≥18 | Allogeneic BM-MSCs | i.v.; 2–3/kg |
24 | Safety; insulin reserve; challenge test | NR | |
| NCT02057211 | II | n = NR; 18–40 | Autologous MSCs | i.v.; NR |
24 | C-peptide | NR | |
| NCT01322789 | I/II | n = NR; 12–35 | Allogeneic BM-MSCs | i.v. (×8); NR |
84 | Safety; insulin; C-peptide; HbA1c; anti-GAD antibody; immune reconstitution | NR | |
| NCT02940418 | I | n = NR; 18–35 | Allogeneic AD-MSCs and autologous BM-MNCs | i.v. (×2); 1 and 10 /kg; |
9 | Safety | NR | |
| NCT01374854 | I/II | n = 21 + 21; 18–40 |
Allogeneic UC-MSCs and autologous BM-MNCs | i.a.; 1.1/kg; |
96 | Safety; insulin; C-peptide; HbA1c; complications | 1-year follow-up: ↑ C-peptide (106 %), ↓ HbA1c (12.6%), ↓ exogenous insulin (29.2%). 8-year follow-up: lower rates of neuropathy (7,1% vs 46,7%), nephropathy (7,1% vs 40,0%), retinopathy (7.1% vs 33.3%) and any complication (14,3% vs 73,3%) [184,185] |
|
| NCT01219465 | I/II | n = NR; 3–35 |
Allogeneic UC-MSCs | i.v.; 20 |
3 | Insulin; C-peptide; HbA1c; immune reconstitution | NR | |
| NCT06407297 | I/II | n = 24; 8–18 |
Allogeneic UC-MSCs | i.v.; dose escalation |
4 | Safety; insulin; C-peptide; HbA1c; immune profile | NR | |
| NCT01157403 | I/II | n = NR; 10–40 | Autologous BM-MSCs | i.v.; 2.5/kg |
24 | Safety; C-peptide | NR | |
| NCT03406585 | I/II | n = 9; 18-40 |
Allogeneic WJ-MSCs (ProTrans) | i.v.; 25/100/ 200 |
12 | Safety; insulin independence; C-peptide; HbA1c | C-peptide maintained (medium or high dose administrated) [186] | |
| NCT03973827 |
I/II | n = 10; 18–40 | Allogeneic WJ-MSCs (ProTrans) | i.v.; 200 |
12 |
Insulin independence; C-peptide; HbA1c | ↓ C-peptide 10% vs 47% (placebo). 7-year additional follow-up: preserved 60% insulin production vs 15% (placebo) [187] |
|
Abbreviations: AD-MSCs – adipose-derived mesenchymal stromal cells; cells; BM-MSCs – bone marrow-derived mesenchymal stromal cells; UC-MSCs – umbilical cord-derived mesenchymal stromal cells; WJ-MSCs – Wharton's jelly-derived mesenchymal stromal cells; BM-MNCs – bone marrow-derived mononuclear cells; i.a. – intra-arterial; i.v. – intravenous; HbA1c – glycated hemoglobin; NR – Not Reported.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.