

Submitted:
01 October 2026
Posted:
02 October 2026
You are already at the latest version
Abstract
Introduction: Genetic variants in the Tenascin-XB (TNXB) gene have been associated with autosomal recessive Ehlers-Danlos Syndrome (classical-like) without vascular features. Here, we report the contribution of two TNXB variants, in cis or trans, to the development of arterial aneurysms and bicuspid aortic valves with or without connective tissue disease features present. Methods: The identification of compound heterozygosity in TNXB (c.8791+1G>A, c.12469+2T>C) in a 52-year-old female with fibromuscular dysplasia, bilateral vertebral artery dissections, and thoracic aortic aneurysm by whole exome sequencing (WES) prompted screening for TNXB variants in an institutional WES registry comprising 350 individuals with aneurysms and/or dissections. Multigene panel testing (MGPT) results from 1844 individuals tested at Ambry Genetics for a personal or family history of aneurysms, dissections, or other connective tissue disease features were used for replication analysis. Random exomes of 26,922 unaffected individuals were used as controls. Statistical analysis using Fisher’s exact test was carried out to compare the frequency of two or more TNXB variants in cases vs. controls. AlphaFold3 structural modeling was used to assess the effects of variants in cis on the 3-D structure and molecular interaction with the TGF-beta-3 proprotein. Results: There were significantly higher numbers of individuals who carried two or more rare, nonsynonymous TNXB variants, in cis or trans, in both WES (n=5/350; 1.4%) and MGPT (n=19/1844, 1.0%) datasets (p<0.01) compared to ethnically matched controls (n=89/26922; 0.14%). Additionally, there was a significantly higher prevalence of bicuspid aortic valve (BAV) in the MGPT cohort compared to the general population (11% vs. <2 % reported). The analysis by AlphaFold3 structural modeling revealed increased distortion of the 3-D structure caused by the presence of two variant(s) in cis vs. one variant in TNXB. Conclusion: This data strongly suggests an association between vascular aneurysm and/or dissection or bicuspid aortic valves and individuals with two TNXB variants.
Keywords:
vascular EDS
; vascular aneurysm
; vascular dissection
; connective tissue disease
1. Introduction
Aneurysms and dissections are among the most lethal inherited vascular diseases in humans (Pál, 2020; Melvinsdottir, 2016; Mehta, 2002). The most common location for aneurysms is the aorta (Norman, 2010), but aneurysms can occur in many other blood vessels, including the carotid artery, coronary arteries, and the vasculature of the brain. If not detected and treated early, aneurysms carry a major risk for dissection, which may lead to long-term neurological deficits, symptoms that vary depending on anatomical region, or death (Sen, 2021; Pál, 2020; Gaul, 2008).
Early diagnosis and intervention remain crucial in reducing mortality from vascular dissections (Elefteriades, 2012, 2014, 2020), but variability in the age of onset and pleiotropy limits the identification of at-risk individuals by clinical examination or imaging alone (Mani, 2010). Thus, the discovery of the genetic underpinning of this disorder can play a crucial role in early diagnosis and intervention and can provide a unique opportunity for a better understanding of disease pathogenesis. The genetics of vascular dissections are complex and incompletely understood. Consequently, our current knowledge of the genetic causes of vascular dissection is mostly limited to syndromic forms of thoracic aortic aneurysms and dissections. Within this subgroup, only 30% of individuals will have a formal genetic diagnosis (Faggion, 2019). With few exceptions, the genetic causes of vascular dissection of non-aneurysmal vessels have remained elusive.
Bicuspid aortic valve (BAV) is the most common valvular congenital heart disease, with a prevalence of 0.5-2% in the general population. BAV has been observed in isolated and syndromic forms and has a wide spectrum of clinical presentations ranging from silent malformation to severe or fatal cardiac events such as increased risk for aortic aneurysm (Tessler, 2021). Except for variants in NOTCH1, ROBO4, GATA4, and GATA5 genes (Giusti, 2017) that account for a small fraction of cases, the genetic cause of isolated BAV remains largely unknown. The advent of next-generation sequencing technologies (NGS) has facilitated the discovery of disease genes, which in turn has increased the power for early identification of individuals at risk (Isselbacher 2016, Gawinecka 2017). In this study, we explored the genetic causes of arterial aneurysms and BAV in independent cohorts. We found strong signal for the association of TNXB with both traits.
Genetic variants in the Tenascin-XB (TNXB) gene have been associated with autosomal recessive classical-like Ehlers-Danlos Syndrome (clEDS) without vascular features. Major criteria of clEDS include skin hyperextensibility with velvety skin texture, generalized joint hypermobility, and easy or spontaneous bruising of the skin. Minor criteria of clEDS include a variety of hand and foot anomalies, atrophy of the muscles of the hands and feet, edema in the legs, mild proximal and distal muscle weakness, axonal polyneuropathy, and vaginal, uterus, and/or rectal prolapse (van Dijk, 2022). A more recent study published last year (Radler, 2025) suggested an association between single TNXB variants and arterial aneurysmal disease and used AlphaFold3 structural modeling to demonstrate the effect. It is proposed TNXB regulates TGF-β/Smad signaling through interactions between FBG-like domain and the latent TGF-β complex, facilitating TGF-β release and receptor activation, although exact mechanisms are unknown (Alcaraz, 2014). Here, we present a brief case report and the results from subsequent case-control analyses that demonstrated a strong association between the presence of two or more variants in TNXB and vascular aneurysms and/or dissections. We also show the utilization of AlphaFold3 structural modeling to demonstrate the varying effect that one variant versus two in cis may have on the overall TNXB protein structure and its interactions with the TGF-beta-3 proprotein. The utilization of this technology is suggestive of the deleterious effect of having two or more variants in cis in the TNXB gene. The findings reported in this manuscript highlight the co-occurrence of two TNXB variants and vascular phenotypes.
2. Methods
We retrospectively reviewed the results from 350 individuals with documented personal and/or family history of aneurysm and/or dissection involving one or more arterial vascular beds, who completed whole-exome genetic testing through Yale DNA Lab between 2014 and 2019. No additional study-specific inclusion or exclusion criteria were utilized. Sequencing was performed using the Illumina platform. GATK best practices were applied to identify genetic variants. The variants were annotated by ANNOVAR and a custom pipeline that includes allele frequencies, OMIM and ClinVar citations, and numerous in silico attributes. The variants were filtered based on their allele frequency of <1% in the public databases (gnomAD and ExAC), information in disease-specific databases, and in silico prediction of their effects on mRNA splicing or protein function, and the conservation of the substituted amino acids, including CADD score, SIFT, and PolyPhen predictions. Variant interpretation followed the American College of Medical Genetics and Genomics (ACMG) guidelines for the classification of variants (Richards, 2015). Identified TNXB variants were carefully evaluated to exclude misalignment or pseudogene-derived artifacts from the highly homologous TNXA locus. Sequence reads were aligned using stringent mapping parameters, and all candidate variants were manually inspected in the Integrative Genomics Viewer (IGV). Only variants supported by uniquely mapped reads with high mapping quality and consistent read distribution were retained. Potentially relevant variants with low quality or lying in poorly mapped regions were confirmed with Sanger sequencing.
The replication dataset was provided by Ambry Genetics and consisted of multigene panel testing (MGPT) results of 1844 individuals with a personal or family history of aneurysm and/or dissection obtained between December 2018 and October 2020. This panel analyzes 35 genes associated with thoracic aortic aneurysms and dissections (TAAD), Marfan syndrome, or related connective tissue disorders and includes the genes ACTA2, BGN, CBS, CHST14, COL1A1, COL1A2, COL3A1, COL5A1, COL5A2, EFEMP2, FBN1, FBN2, FKBP14, FLNA, FOXE3, LOX, MAT2A, MED12, MFAP5, MYH11, MYLK, NOTCH1, PLOD1, PRDM5, PRKG1, SKI, SLC2A10, SMAD3, SMAD4, TGFB2, TGFB3, TGFBR1, TGFBR2, TNXB and ZNF469.
The control dataset was also provided by Ambry Genetics and consisted of 26,922 WES results from individuals with no history of aneurysm or dissection. Rare TNXB variants that passed bioinformatic quality filtering were queried. When available, laboratory-determined variant classifications were based on published guidelines by the ACMG (https://www.ambrygen.com/science/variant-classification, Richards, 2015). For unclassified alterations, we used a threshold based on penetrance, prevalence, and genetic contribution to disease to rule out variants that are too common in the population to cause disease, as determined by Popmax filtering allele frequencies in gnomAD. An additional 146 exomes from clinical and research exome data available at Yale Cardiovascular Genetics Program were used in the statistical analysis as ethnically matched controls, bringing the total number of controls to 27,068. Control data was not generated under a single standardized sequencing protocol. Gene transcript information was not available for all cases from the Ambry and Yale cohorts.
In a separate analysis, WES results of 158 Caucasian individuals with isolated BAV were screened for TNXB variants. Table S1 provides a summary of the different datasets included in the analysis. Principal Component Analysis (PCA) was used to rule out population stratification. The dataset yielded a little over 14 million different variants amongst all individuals. These variants were filtered to 10,061 based on LD and degree of missingness. The R package missMDA was then used to impute missing values, followed by PCA analysis using the R package FactoMineR. The first three principal components were graphed against each other to exclude population stratification. Fisher’s exact test was used as the statistical tool to compare the burden of multiple TNXB variants in cases vs. controls.
AlphaFold3 structural modeling was used to visualize predicted changes in structure and interaction between TNXB and the TGF-β3 proprotein (the precursor of latency-associated peptide and transforming growth factor beta-3) with one versus multiple TNXB variants present in cis. Case #2 from Table S2, in which phasing was available and indicated inheritance through a single lineage, was used to demonstrate this. AlphaFold3 was run with each TNXB variants present independently (p.Thr3173Ser and p.Tyr1945His), both variants present together and the reference TNXB with no variant present. Each TNXB version was run with TGF-beta-3 proprotein. The structures were loaded into PyMOL to visualize the interactions between TNXB and TGF-beta-3 proprotein. Interface residues were defined as residues having at least one atom within 4.5Å of the opposing chain. The number of hydrogen bonds at the TNXB mutation sites was also examined and compared to the non-mutated protein.
3. Results
3.1. Case Presentation
A 52-year-old female was diagnosed with bilateral vertebral artery dissection, fibromuscular dysplasia, and an aortic aneurysm (Figure 1). She was found to have a right and left vertebral artery dissection within a singular week. Two years later, she was diagnosed with an ascending aortic aneurysm, measuring 45 x 41 mm by MRI. Her medical history included a Tetralogy of Fallot that was repaired. Examination revealed joint hypermobility in her fingers and a high arched palate. Physical exam did not reveal any other major or minor criteria of clEDS. Her son reportedly had mild joint hypermobility, but there was limited information on the remaining family history.
She underwent WES, where variants in genes associated with aneurysms, dissections, and connective tissue disease were evaluated following the ACMG guidelines for variant interpretation. Two variants were found in the TNXB gene, c.8791+1G>A (likely pathogenic) and c.12469+2T>C (VUS). No variants of uncertain significance (VUS), likely pathogenic, or pathogenic variants were found in any other gene. Segregation analysis in a first-degree relative confirmed that the variants were in trans (biallelic). This finding prompted the analysis of two larger cohorts with arterial aneurysms
3.2. Data Analysis
The demographics for all individuals with ≥ 2 TNXB variants are shown in Table S1. The mean age at time of testing was 56.3 years for WES cases and 43.37 years for MGPT cases. Principal component analysis excluded population stratification as shown in Figure 2 for the first three principal components, plotting the individuals with ≥ 2 TNXB variants (highlighted in blue) against controls (highlighted in red).
3.3. The Analysis of the WES Dataset for Genetic Variants Associated with TAAD
Of the 350 WES results reviewed for individuals with TAAD, 60.6% (n=212) had a negative result with no reportable findings. The remaining 39.4% (n=138) had one or more reportable pathogenic, likely pathogenic variants, or VUS. The most frequently identified genes for individuals with aneurysm and/or dissection were, in order of frequency: FBN1, NOTCH1, FBN2, COL5A1, COL5A2, and MYH11, followed by TNXB (Figure 3). In total, 7.2% (n=10/138) of cases were found to have one or more reportable variants in TNXB, and half of these (n=5/10) had two variants. There were 10 unique variants in total, which included 7 missense, and 3 splice site variants. Out of these variants, 9 were classified as variants of uncertain significance. No nonsense variants or indels were identified.
All five individuals who carried two TNXB variants had a personal diagnosis of aneurysms and/or dissections, and three of the five had other additional features of connective tissue disease summarized in Table S1 and Table S2. Fisher’s Exact Test demonstrates a significant difference in the presence of >2 TNXB variants between WES cases and controls (p<0.01).
3.4. Analysis of the Replication Cohort
A review of results from 1844 TAADNext multigene panels completed at Ambry Genetics revealed 27 individuals (1.0%) that carried two or more TNXB variants. Of these 27 individuals, 19 (n=19/27) of them were not identified to have any other variant that was classified as pathogenic, likely pathogenic, or VUS. From this, 68% (n=13/19) had a personal history of vascular aneurysms and/or dissections, and 42% (n=8/19) had other features of connective tissue disease, summarized in Table S1 and Table S3. Additionally, there were three individuals with Marfanoid features, of whom two had only a family history of aneurysm and/or dissection, and there was no additional information available for the third. There were 43 different variants in 27 individuals, which included 36 different missense variants, one frameshift variant, and one deletion. Five variants were present in more than one individual. Interestingly, one extremely rare variant (AF: 3.1e-5) was present in both the WES dataset and MGPT case dataset. All variants, aside from one, were classified as variants of uncertain significance. Fisher’s Exact Test demonstrates a significant difference in the presence of >2 TNXB variants between MGPT cases and controls (p<0.01). The zygosity was not assessed for most cases as definitive phasing was unavailable, but in a few individuals from the Ambry cohort, the inheritance could be traced through a single ancestry lineage, suggesting that variants are in cis in these individuals.
3.5. The association between TNXB variants and Bicuspid Aortic Valve (BAV):
From the 27 individuals with two or more variants in TNXB identified in the MGPT case dataset, 3 reported a clinical diagnosis of BAV (Table S2, cases # 9, 15, and 18). This prompted the WES of 158 individuals with isolated BAV. The analysis identified 3 individuals with 2 or more TNXB variants (Table S4). The mutations were verified by Sanger sequencing (Figure 4). Fisher’s Exact Test demonstrated a significant difference in the presence of >2 TNXB variants between BAV cases and controls (p<0.01).
3.6. Interactions Between TNXB and TGF-beta-3 Proprotein Visualized with AlphaFold and PyMOL:
Protein structures were generated by AlphaFold3 followed by interaction analyses using PyMOL. This revealed alterations in the TNXB–TGF beta-3 proprotein interface when no mutations, one mutation, and two mutations were present in TNXB (Figure 5). With the absence of mutations in TNXB, interactions between TNXB and TGF-beta-3 proprotein were subtle and spatially constrained. Introduction of the p.Thr3173Ser mutation resulted in marked conformational changes within TNXB, accompanied by an increase in interactions with TGF-beta-3 proprotein that fell within 4.5 Å. The p.Tyr1945His variant induced comparatively modest structural changes; however, the introduction of both variants caused notable changes in TNXB structure and augmented its interactions with TGF-beta-3 proprotein. These findings suggest a synergistic effect of the two TNXB variants.
Additionally, with the p.Thr3173Ser variant, there is a loss of a hydrogen bond at the mutation site (Figure 6). In contrast, the p.Tyr1945His variant shows no change in number of hydrogen bonds at the mutation site. With the loss of the hydrogen bond for p.Thr3173Ser indicating a potential increase in instability, this may explain the more notable changes in TNXB structure compared to the p.Tyr1945His variant.
4. Discussion
Homozygous variants in TNXB are associated with autosomal recessive Ehlers-Danlos Syndrome (classical-like) and autosomal dominant vesicoureteral reflex 8, which share traits such as joint hypermobility without any known vascular aneurysms or dissections (OMIM 2018). One study from 2019 (Micale, 2019), identified two individuals with TNXB-clEDS due to compound heterozygosity for null alleles in TNXB. Both individuals had soft and hyperextensible skin, generalized joint hypermobility, and related musculoskeletal complications. In addition, one of the individuals displayed somewhat of a vascular phenotype with recurrent subconjunctival hemorrhages and spontaneous rupture of the brachial vein, suggesting a potential relationship between TNXB-clEDS and vascular fragility. Previous studies have also suggested a causal relationship between TNXB haploinsufficiency and hypermobile-type Ehlers-Danlos syndrome and have reported that patients who are heterozygous for the tenascin-X mutation may or may not exhibit features of hypermobility (Zweers, 2003). Furthermore, joint hypermobility associated with vascular Ehlers-Danlos syndrome (vEDS) or other connective tissue diseases can be subtle or even absent in some patients (Sobey, 2014). This points to a high degree of variability in phenotypes based on zygosity.
Our data demonstrate a strong association between the presence of two or more TNXB variants, whether in cis or trans, and the occurrence of vascular aneurysms, dissections, and bicuspid aortic valve, with or without additional features of connective tissue disease. These findings suggest an expansion of the clinical phenotype associated with TNXB variants beyond the currently established association with clEDS, which is not presently recognized as having a vascular component. Future In vivo and in vitro functional studies will be required to confirm the predicted effects of multiple vs. single variants demonstrated by our AlphaFold3 protein models and to determine if the variants can independently contribute to disease. The absence of such functional studies represents a limitation of the present study. The possibility of linkage disequilibrium and the presence of multiple variants indicating general genetic instability at this locus should also be considered.
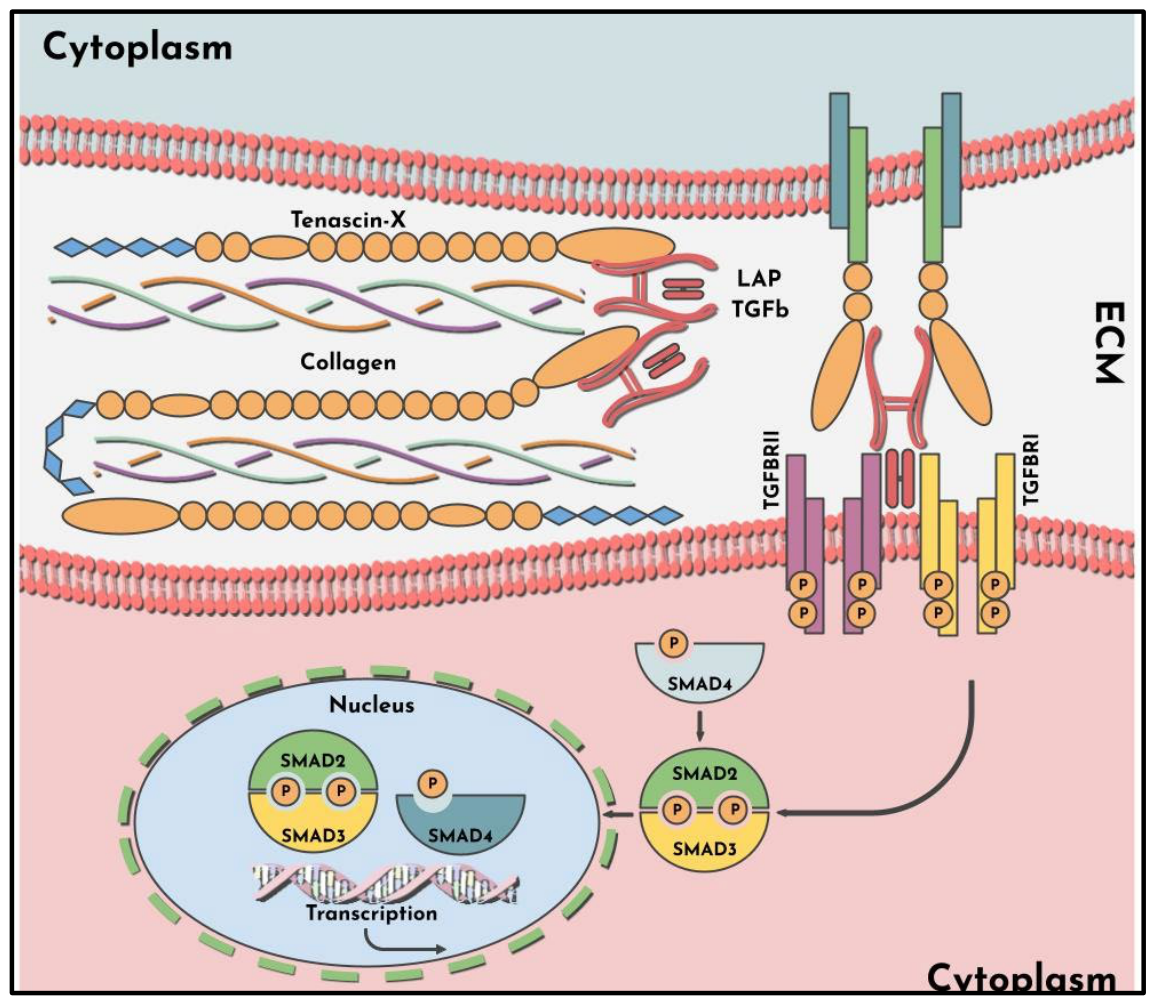
Although the exact molecular mechanism is unknown, the TNX fibrinogen-like domain of TNXB has been shown to activate the TGF-β signaling pathway, an important regulator of collagen production involved in connective tissue diseases, including vascular phenotype (Figure 7). Studies have shown that TNXB interacts with the latent LAP·TGF-β complex in vitro and in vivo and induces TGF-β/Smad intracellular signaling (Figure 7). It is proposed that the FBG-like domain of TNXB is cleaved and is anchored to integrins, which induces conformational changes to the latent complex and promotes the release of TGF-β and the activation of TGFβRI and II in the adjacent cells (Alcaraz, 2014). It is important to note that precise mechanisms underlying conformational changes of and interactions between TNXB and the LAP·TGF-β complex are not fully understood. Altered activities of the TGF-β pathway have been associated with syndromic aortic aneurysms such as Marfan and Loeys-Dietz syndromes (Takeda, 2018). Our protein models generated with AlphaFold3 and PyMOL demonstrate significant conformational changes in TNXB and its interaction with LAP when two variants are present, compared to the wild-type protein or when a single variant is present. We speculate that the most significant contribution to the conformational changes of TNXB may result from the loss of a hydrogen bond, which can cause an increase in instability. Based on these models, we hypothesize that the conformational changes of TNXB and its ensuing increased interactions with TGF-beta-3 proprotein, when two or more variants are present, trigger LAP release of TGF-β. In summary, the modeling suggests a greater impact of two mutations in cis conformation versus one and may explain the association with vascular traits. Our provided case report is supportive of an association with two variants in trans and vascular traits.
Strikingly, most individuals with two or more variants in TNXB in the MGPT dataset had a personal history of aneurysm or dissection. These individuals displayed a high degree of variability in phenotype in terms of age of onset, types, location of aneurysm or dissection, family history, and additional connective tissue disease features. While definitive phasing could not be confirmed, in a few instances, the inheritance could be traced through a single ancestry lineage, suggesting that variants are in cis in these individuals. Interestingly, the presence of 2 variants in cis in genes such as TNXB (Zweers, 2003), MYBPC3 (Viswanathan, 2018), and MYH7 (Blair, 2001) have been associated with increased disease risk. Across the cases and the cohorts, the identified variants were located in different domains, suggesting additive effects on the overall function of the protein.
While burden analysis used in our study does not exclude the presence of other unidentified genetic causes for the aneurysms and dissections in patients with multiple TNXB mutations, the novelty and/or very low allele frequency of the variants, and the absence of reportable variants in any other known disease gene suggests their contribution to disease development. It is important to note that most variants identified in this study were classified as variants of uncertain significance; therefore, their contribution to observed phenotypes remains uncertain. Nevertheless, these variants were prioritized through a stringent filtering strategy incorporating rarity, predicted functional impact, and clinical relevance, suggesting they warrant further thought and investigation.
In conclusion, our data highlights the co-occurrence of two TNXB variants and incidence of arterial aneurysm, dissection, and bicuspid aortic valve and is supportive of an association between multiple TNXB variants in cis or trans and vascular disease with or without additional connective tissue disease features. Future studies incorporating both functional validation and allelic phasing will be necessary to confirm these findings and better define the underlying molecular mechanisms. Incorporating TNXB into genetic testing panels for aneurysms and arterial dissections will facilitate validation of its disease relevance, enable assessment of genotype–phenotype correlations, and ultimately improve genetic screening and risk stratification of individuals at risk.
Supplementary Materials
The supplementary information is available through the Zenado open repository https://doi.org/10.5281/zenodo.19455873.
Author Contributions
Study design and writing: L.C, A.N; data collection, extraction, and analysis: L.C, A.N, M.T, D.J.D, J.M.R, Y.L, S.M, M.F; pathway analysis and images: J.M.R, K.M, A.M; Review and editing: L.C, A.N, M.T, D.J.D, A.E.B, A.M.
Funding
This work was supported by grants from the National Institutes of Health ID #R01HL171054 and ID#R01DK134329 to Arya Mani.
Institutional Review Board Statement
IRB approval was obtained for this study from Yale University under IRB#0108012622 on 27 October 2025.
Informed Consent Statement
All the procedures performed in studies involving our human participants were in accordance with the ethical standards of our institutions and with the 1964 Helsinki Declaration and its later amendments or comparable ethical standards. For the samples acquired from Ambry: The WGC Institutional Review Board (formerly the Western Institutional Review Board) determined the study to be exempt from the Office for Human Research Protections Regulations for the Protection of Human Subjects (45 CFR 46) and provided a waiver of consent for these deidentified data. For the samples acquired from Yale: Informed consent was obtained from Yale study participants.
Data Availability Statement
Ambry deposits classified alterations identified during diagnostic testing into ClinVar (https://www.ncbi.nlm.nih.gov/clinvar/).
Conflicts of Interest
John Michael Ranola is a salaried employee of Ambry Genetics. Meghan Towne was a salaried employee of Ambry Genetics at the time the manuscript was prepared and is currently a salaried employee of Ionis Pharmaceuticals. She has not contributed to or worked on the manuscript in her current role at Ionis Pharmaceuticals. Arpita Neogi was an employee of Yale University at the time the manuscript was prepared and is currently a salaried employee of GeneDx. She has not contributed to or worked on the manuscript since beginning her role at GeneDx. No other authors have conflicts of interest to disclose.
References
- Pal, D.; Szilagyi, B.; Berczeli, M.; et al. Ruptured Aortic Aneurysm and Dissection Related Death: an Autopsy Database Analysis. Pathol. Oncol. Res. 2020, 26(4), 2391–2399. [Google Scholar] [CrossRef] [PubMed]
- Mehta, R.H.; Suzuki, T.; Hagan, P.G.; et al. Predicting death in patients with acute type a aortic dissection. Circulation 2002, 105(2), 200–206. [Google Scholar] [CrossRef] [PubMed]
- Melvinsdottir, I.H.; Lund, S.H.; Agnarsson, B.A.; Sigvaldason, K.; Gudbjartsson, T.; Geirsson, A. The incidence and mortality of acute thoracic aortic dissection: results from a whole nation study. Eur. J. Cardiothorac. Surg. 2016, 50(6), 1111–1117. [Google Scholar] [CrossRef] [PubMed]
- Norman, P.E.; Powell, J.T. Site specificity of aneurysmal disease. Circulation 2010, 121(4), 560–568. [Google Scholar] [CrossRef] [PubMed]
- Sen, I.; Erben, Y.M.; Franco-Mesa, C.; DeMartino, R.R. Epidemiology of aortic dissection. Semin Vasc. Surg. 2021, 34(1), 10–17. [Google Scholar] [CrossRef] [PubMed]
- Gaul, C.; Dietrich, W.; Erbguth, F.J. Neurological symptoms in aortic dissection: a challenge for neurologists. Cerebrovasc. Dis. 2008, 26(1), 1–8. [Google Scholar] [CrossRef] [PubMed]
- Ziganshin, B.A.; Rajbanshi, B.G.; Tranquilli, M.; Fang, H.; Rizzo, J.A.; Elefteriades, J.A. Straight deep hypothermic circulatory arrest for cerebral protection during aortic arch surgery: Safe and effective. J. Thorac. Cardiovasc Surg. 2014, 148(3), 888-898; discussion 898-900. [Google Scholar] [CrossRef] [PubMed]
- Ziganshin, B.A.; Bailey, A.E.; Coons, C.; et al. Routine Genetic Testing for Thoracic Aortic Aneurysm and Dissection in a Clinical Setting. Ann. Thorac. Surg. 2015, 100(5), 1604–1611. [Google Scholar] [CrossRef] [PubMed]
- Keramati, A.R.; Sadeghpour, A.; Farahani, M.M.; Chandok, G.; Mani, A. The non-syndromic familial thoracic aortic aneurysms and dissections maps to 15q21 locus. BMC Med. Genet. 2010, 11, 143. [Google Scholar] [CrossRef] [PubMed]
- Faggion Vinholo, T.; Brownstein, A.J.; Ziganshin, B.A.; et al. Genes Associated with Thoracic Aortic Aneurysm and Dissection: 2019 Update and Clinical Implications. Aorta 2019, 7(4), 99–107. [Google Scholar] [CrossRef] [PubMed]
- van Dijk, F.S.; Ghali, N.; Demirdas, S.; et al. TNXB-Related Classical-Like Ehlers-Danlos Syndrome. In GeneReviews® [Internet]; Adam, M.P., Mirzaa, G.M., Pagon, R.A., et al., Eds.; University of Washington: Seattle (WA); Seattle, 15 Sep 2022; Available online: https://www.ncbi.nlm.nih.gov/books/NBK584019/.
- Demirdas, S.; Dulfer, E.; Robert, L.; Kempers, M.; van Beek, D.; Micha, D.; van Engelen, B.G.; Hamel, B.; Schalkwijk, J.; Loeys, B.; Maugeri, A.; Voermans, N.C. Recognizing the tenascin-X deficient type of Ehlers-Danlos syndrome: a cross-sectional study in 17 patients. Clin. Genet. 2017, 91(3), 411–425. [Google Scholar] [CrossRef] [PubMed]
- Richards, S.; Aziz, N.; Bale, S.; et al. Standards and guidelines for the interpretation of sequence variants: a joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology. Genet Med. 2015, 17(5), 405–424. [Google Scholar] [CrossRef] [PubMed]
- Zweers, M.C.; Bristow, J.; Steijlen, P.M.; et al. Haploinsufficiency of TNXB is associated with hypermobility type of Ehlers-Danlos syndrome. Am. J. Hum. Genet. 2003, 73(1), 214–217. [Google Scholar] [CrossRef] [PubMed]
- Alcaraz, L.B.; Exposito, J.Y.; Chuvin, N.; et al. Tenascin-X promotes epithelial-to-mesenchymal transition by activating latent TGF-beta. J. Cell Biol. 2014, 205(3), 409–428. [Google Scholar] [CrossRef] [PubMed]
- Neptune, E.R.; Frischmeyer, P.A.; Arking, D.E.; et al. Dysregulation of TGF-beta activation contributes to pathogenesis in Marfan syndrome. Nat. Genet. 2003, 33(3), 407–411. [Google Scholar] [CrossRef] [PubMed]
- Hara, H.; Takeda, N.; Fujiwara, T.; et al. Activation of TGF-beta signaling in an aortic aneurysm in a patient with Loeys-Dietz syndrome caused by a novel loss-of-function variant of TGFBR1. Hum. Genome Var. 2019, 6, 6. [Google Scholar] [CrossRef] [PubMed]
- Isselbacher, E.M.; Lino Cardenas, C.L.; Lindsay, M.E. Hereditary Influence in Thoracic Aortic Aneurysm and Dissection. Circulation 2016, 133(24), 2516–2528. [Google Scholar] [CrossRef] [PubMed]
- Viswanathan, S.K.; Puckelwartz, M.J.; Mehta, A.; et al. Association of Cardiomyopathy With MYBPC3 D389V and MYBPC3Delta25bpIntronic Deletion in South Asian Descendants. JAMA Cardiol. 2018, 3(6), 481–488. [Google Scholar] [CrossRef] [PubMed]
- Blair, E.; Price, S.J.; Baty, C.J.; Ostman-Smith, I.; Watkins, H. Mutations in cis can confound genotype-phenotype correlations in hypertrophic cardiomyopathy. J. Med. Genet. 2001, 38(6), 385–388. [Google Scholar] [CrossRef] [PubMed]
- Gawinecka, J.; Schonrath, F.; von Eckardstein, A. Acute aortic dissection: pathogenesis, risk factors and diagnosis. Swiss Med. Wkly. 2017, 147, w14489. [Google Scholar] [CrossRef] [PubMed]
- 2018. Online Mendelian Inheritance in Man (OMIM) TNXB, tenascin XB (OMIM Entry No. 600985). Johns Hopkins University. Available online: https://www.omim.org/entry/600985.
- Norgan Radler, C.; Wang, T.; LeGate, J.; Crone, L.; Deo, P.; Wortley, J.; Moore, P.; Bryant, G.; Smitherman, K.; Sathyamoorthy, M. Genetic Variants in the Extracellular Matrix Gene TNXB Predicted to Alter Fibronectin III Domains in Arterial Aneurysmal and Dissection Diseases. Int. J. Mol. Sci. 2025, 26(13), 6535. [Google Scholar] [CrossRef] [PubMed]
- Micale, L.; Guarnieri, V.; Augello, B.; Palumbo, O.; Agolini, E.; Sofia, V.M.; Mazza, T.; Novelli, A.; Carella, M.; Castori, M. Novel TNXB Variants in Two Italian Patients with Classical-Like Ehlers-Danlos Syndrome. Genes. 2019, 10(12), 967. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Figure Magnetic resonance angiogram (MRA) of the neck showing dissection of vertebral arteries. The dissection flap in the V2 segment of the left vertebral artery is shown by arrows in the cross and sagittal sections (1a, 1b). Demonstrated is also a dissection flap in the V2 segment of the right vertebral artery (1c) with more prominent lateral outpouching of the lumen concerning for pseudoaneurysm.
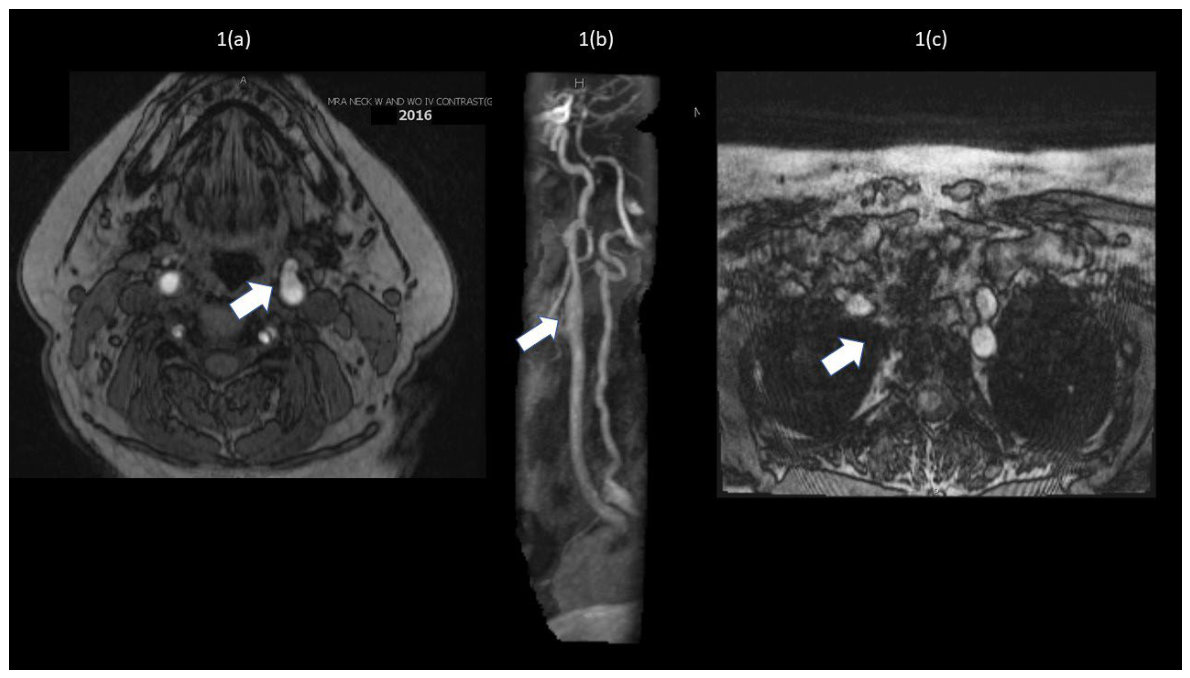
Figure 2.
Principal Component Analysis of first three principal components plotted against each other for individuals with two or more variants in TNXB.
Figure 2.
Principal Component Analysis of first three principal components plotted against each other for individuals with two or more variants in TNXB.
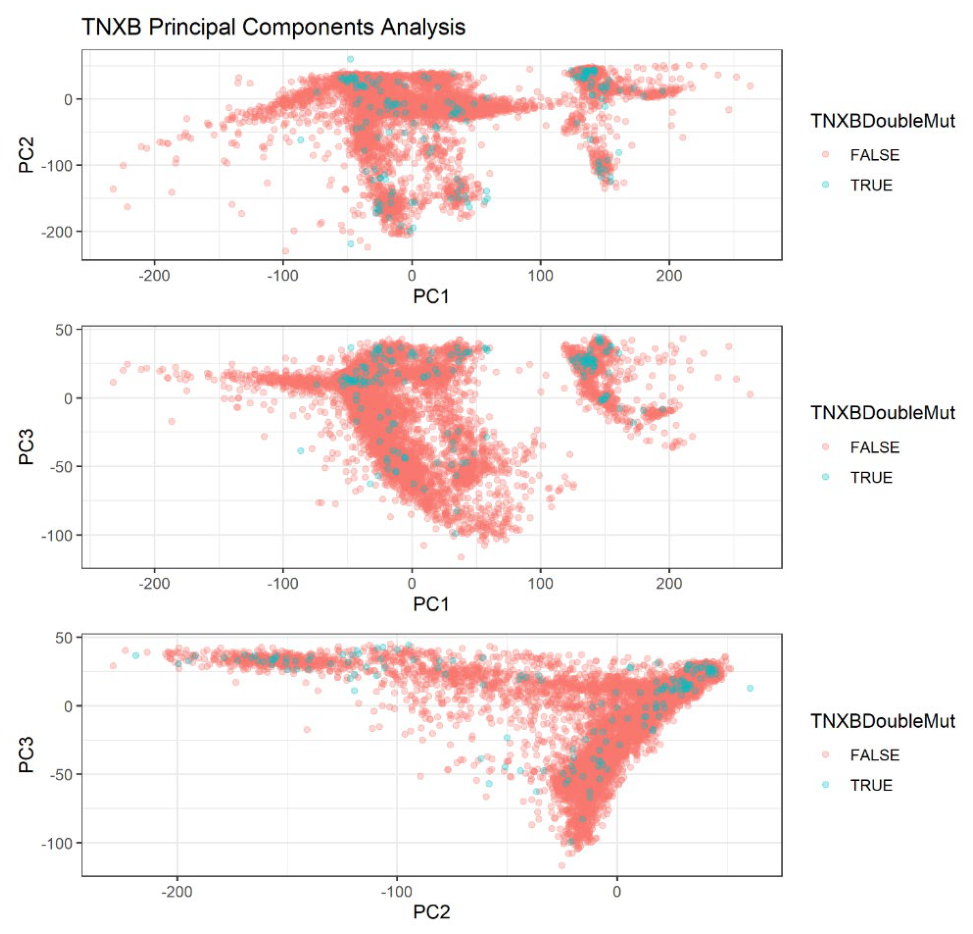
Figure 3.
The frequency distribution of known aneurysm/dissection genes and TNXB amongst clinical WES cases.
Figure 3.
The frequency distribution of known aneurysm/dissection genes and TNXB amongst clinical WES cases.
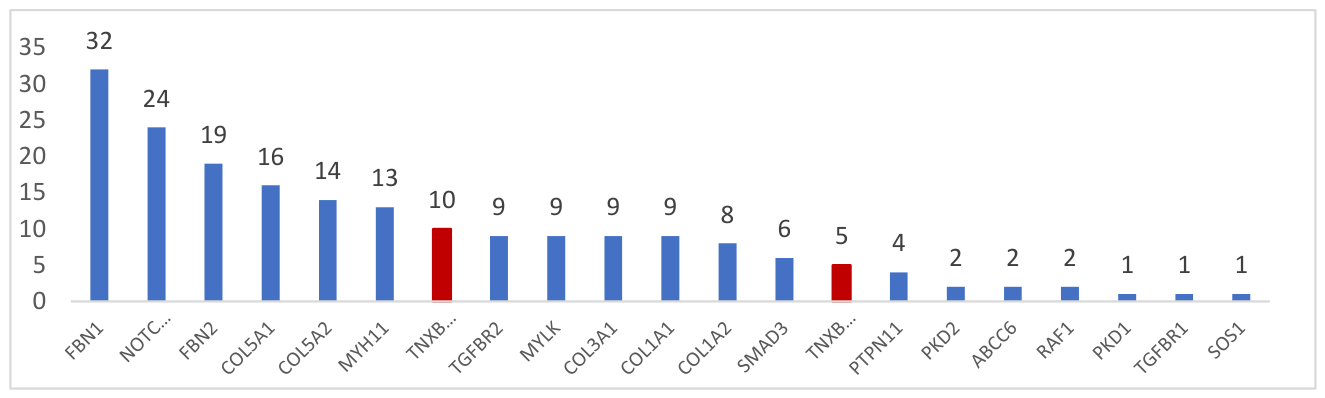
Figure 4.
Sanger sequencing of TNXB variants from BAV cases with two or more TNXB variants.
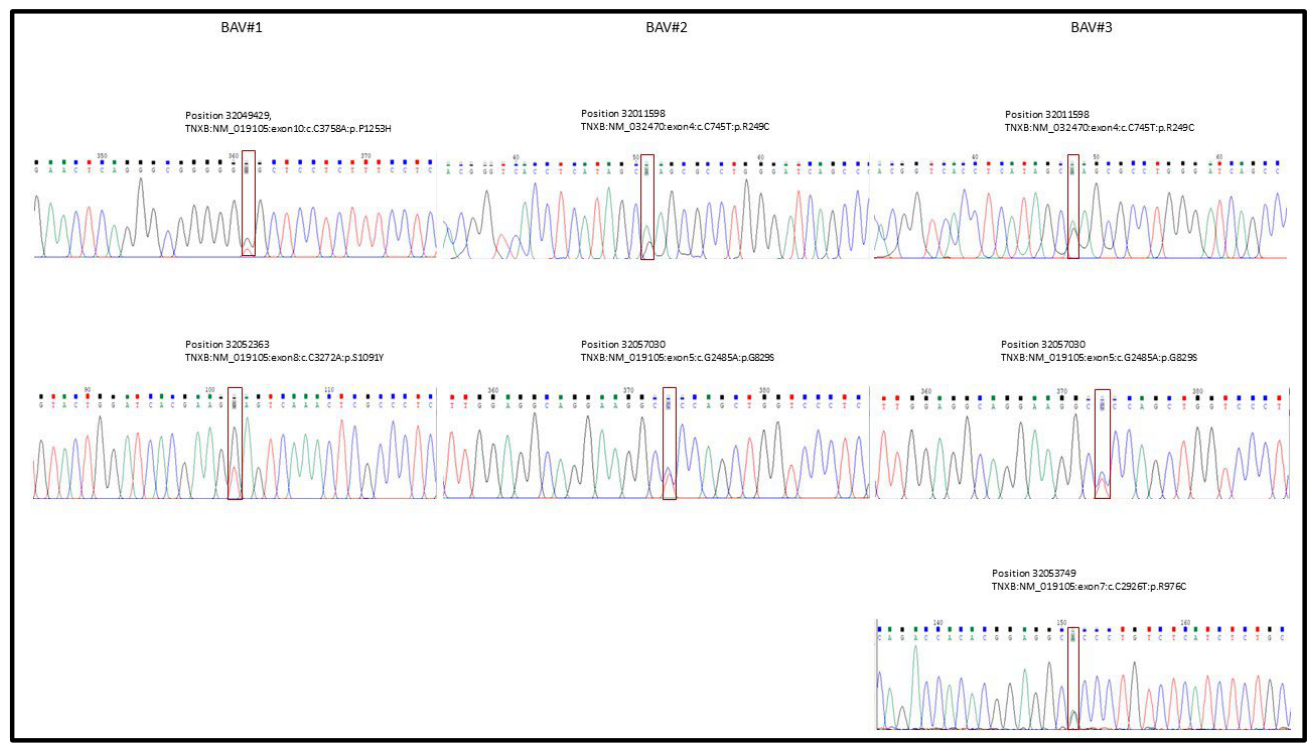
Figure 5.
TNXB and TGF-beta-3 proprotein structures and interactions with no mutations present (A), two different single mutations present (C is p.Thr3173Ser and D is p.Tyr1945His), and the two mutations present together (B). The red indicates interactions between TNXB and TGF-beta-3 proprotein that are within 4.5 Å.
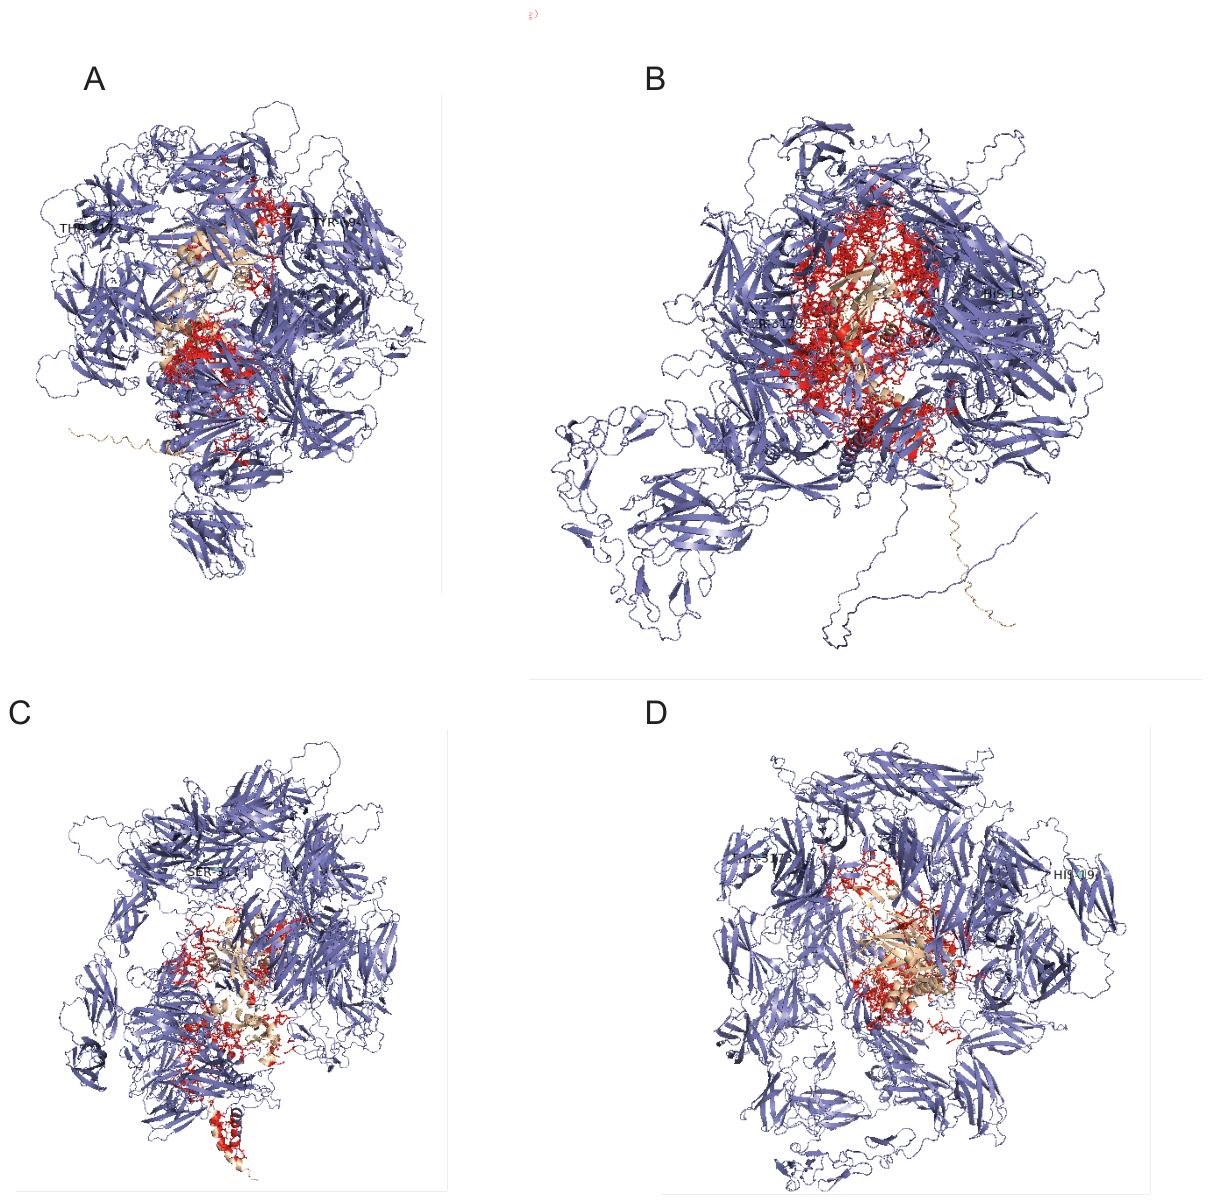
Figure 6.
Hydrogen bonds at the non-mutated amino acid sites (A is Thr3173 and C is Tyr1945) and hydrogen bonds at the mutated amino acid sites (B is Thr3173Ser and D is Tyr1945His) are shown in angstrom (Å) and are labeled with the red dashed line with the corresponding Å.
Figure 6.
Hydrogen bonds at the non-mutated amino acid sites (A is Thr3173 and C is Tyr1945) and hydrogen bonds at the mutated amino acid sites (B is Thr3173Ser and D is Tyr1945His) are shown in angstrom (Å) and are labeled with the red dashed line with the corresponding Å.
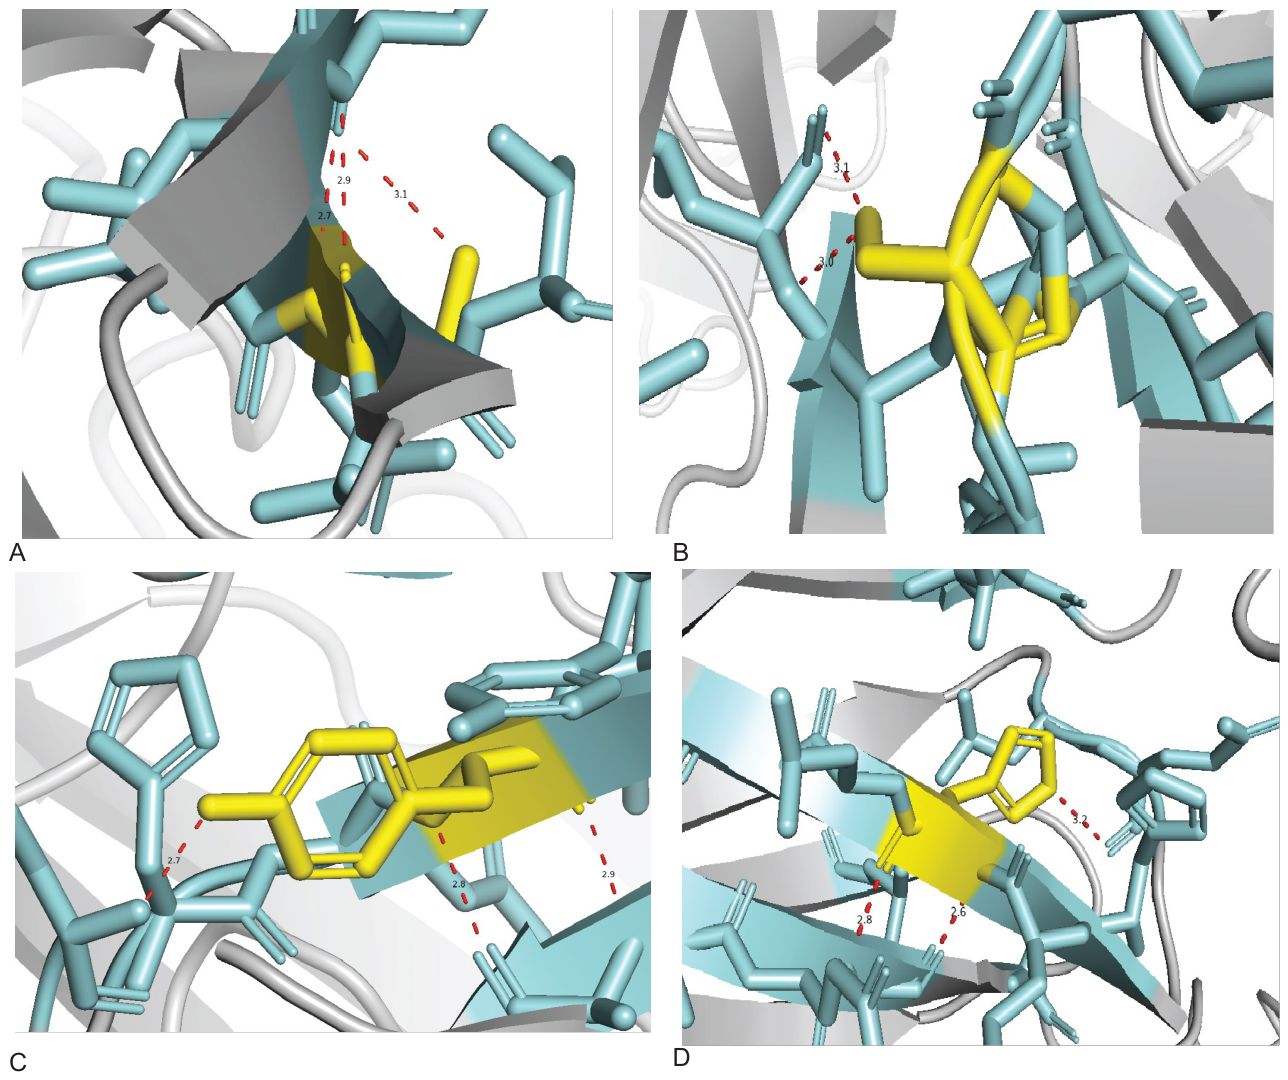
Figure 7.
Interaction between TNXB and connective tissue proteins implicated in aneurysm disorders.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.