

Submitted:
30 September 2026
Posted:
02 October 2026
You are already at the latest version
Abstract
Purpose of Review Trials of non-pharmacological treatment in chronic migraine report inconsistent effects on headache frequency. This review groups recent trials and syntheses by mechanism and asks whether mechanism explains the inconsistency and what it implies for treatment order. Recent Findings A primary-care education and self-management programme (CHESS) improved pain self-efficacy, while headache impact, headache days and medication overuse were unchanged at 12 months. Mindfulness added to withdrawal and prophylaxis (MIND-CM) increased the proportion with at least 50% fewer headache days (78% versus 48%). In chronic migraine with medication overuse, eptinezumab added to brief education reduced monthly migraine days in weeks 1–4 by 3.2 more than placebo (RESOLUTION). Syntheses rate the frequency effects of cognitive-behavioural, relaxation and mindfulness treatments as low-certainty; acceptance-based treatment improved disability without a significant frequency effect, and mindfulness reduced attack frequency slightly. During withdrawal, a nurse-led behavioural programme reduced acute-medication days at week 24 without changing migraine days. Summary Grouped by mechanism, treatments that lower ascending nociceptive drive, including calcitonin gene-related peptide (CGRP) pathway blockade and, on weaker evidence, behavioural treatment of insomnia, reduce headache frequency. Treatments aimed at the appraisal of pain improve self-efficacy and, in several trials, disability; no trial identified isolated their effect on frequency after a documented fall in drive, most tested packages mix both mechanisms, and some trials do not fit. The proposed rule is to start drive-lowering treatment first, behavioural forms included, and to offer interpretation-directed treatment alongside it when waiting is inappropriate. Five falsifiable predictions follow.
Keywords:
chronic migraine
; non-pharmacological treatment
; behavioural treatment
; treatment sequencing
; calcitonin gene-related peptide
; medication-overuse headache
1. Introduction
In 2023, two randomised trials of group-delivered psychological treatment for chronic headache, most participants having migraine, reached opposite conclusions. In the Chronic Headache Education and Self-management Study (CHESS), 736 adults with chronic headache were randomised to a two-day group education and self-management programme with a one-to-one nurse consultation and telephone support, or to usual care with relaxation material; 727 had migraine, either chronic migraine or chronic tension-type headache with episodic migraine. At 12 months there was no difference in headache impact (Headache Impact Test, HIT-6; adjusted mean difference −0.3, 95% CI −1.23 to 0.67) or in headache days (0.9, −0.29 to 2.05) [1]. In the MIND-CM trial, 177 people with chronic migraine and medication-overuse headache all received withdrawal from the overused drug, education and tailored prophylaxis; among those additionally randomised to six sessions of mindfulness, 78.4% reached at least a 50% reduction in headache frequency at 12 months, against 48.3% in the control arm (p < 0.0001) [2].
Intensity, setting, therapist contact and population differ between the two trials, and any of these could explain the difference. A systematic review of this literature found heterogeneity too great to pool and concluded that current evidence does not support educational, behavioural, cognitive and self-management interventions for improving headache-related symptoms and quality of life in chronic migraine, with very limited evidence that they may contribute to reducing headache frequency [3].
This review asks whether the same trials read differently when the treatments are grouped by mechanism. The category under test, non-pharmacological treatment, is defined by what the treatment is not, and it groups together interventions with different proposed mechanisms. Withdrawal of overused acute medication and instruction in acceptance of pain are both classed as behavioural, although they are proposed to act on different parts of the problem, and the review examines whether that difference matters for their place in a sequence.
The review proposes a mechanism-based classification and derives a rule about order from it. Non-pharmacological treatments in migraine can be divided into those proposed to lower ascending nociceptive drive and those proposed to act on how bodily signals are appraised and responded to. That division cuts across the pharmacological and non-pharmacological line on which guidelines, trials and systematic reviews are organised, and it places behavioural medicine in both groups, with support for withdrawal of overused medication and behavioural treatment of insomnia in the first, and cognitive-behavioural therapy, acceptance and commitment therapy and mindfulness in the second. The proposed consequence for sequence is that interpretation-directed treatment reduces attack frequency mainly once drive has been lowered, because loosening a fixed expectation of pain is expected to have little effect on frequency while afferent input continues to support that expectation. The corresponding clinical rule is to start drive-lowering treatment first, pharmacological or behavioural, and to offer interpretation-directed treatment alongside it under the conditions set out in Section 5.
Chronic migraine is the worked case because the ascending pathway has a molecular target in calcitonin gene-related peptide (CGRP) and the outcome can be counted in days, which makes the two classes separately manipulable and an order effect measurable. Trials in episodic migraine, in mixed chronic headache and in adolescents are used where adult chronic-migraine trials are lacking, and they are identified as such. Section 7.3 sets out the limitations.
Several recent reviews cover the same ground from other directions. A review in Current Pain and Headache Reports summarises acupuncture, physical therapy, psychological therapies, biofeedback and neuromodulation modality by modality, with GRADE ratings where available, presents them as alternatives or adjuncts to drug treatment, and rates the effect of psychological therapies as small and the certainty of the evidence as low [4]; an earlier review in the same journal surveyed non-pharmacological options specifically in chronic migraine [5]. A systematic review of 50 trials in adults found low-strength evidence that cognitive-behavioural therapy, relaxation training and mindfulness-based therapies may each reduce attack frequency and that education alone may improve disability; it noted that most interventions were multicomponent and called for "smart study designs" and therapies personalised to individual characteristics [6]. Grazzi and colleagues place psychological treatment within a biopsychosocial account, with patient education as a first step of care and psychological treatment as a means of enhancing the effect of medication [7]. For medication-overuse headache, a 2026 review reframes the disorder as nociplastic, reports that current recommendations favour a stepwise approach beginning with patient education, notes that preventive treatment can be started before or alongside withdrawal, and gives behavioural support a place during and after withdrawal [8]; a perspective on telehealth calls for studies that combine or sequence CGRP-targeted and behavioural treatment [9]. These reviews organise the treatments by modality or by stage of care. The present review adds a grouping by mechanism, from which an order and a set of testable predictions follow.
The idea that one treatment prepares the ground for another has older roots. Patients with chronic, daily, high-intensity headache, a population not restricted to migraine, improved less with biofeedback and relaxation than matched controls with fewer headache days (12.7% against 49.8%), and tended to be more anxious and to report more non-headache somatic complaints [10]; patients with high analgesic consumption responded less well than matched controls to self-regulatory treatment, and the two groups did not differ in current psychological functioning [11]. A trial of behavioural sleep modification in women with transformed migraine stated the hypothesis that treating sleep would reduce headache frequency and revert transformed migraine to episodic migraine [12]. More recently, cognitive-behavioural therapy for insomnia has been recommended as first-line treatment for comorbid insomnia in migraine [13]. In 85 adolescents with chronic pain, greater baseline insomnia was associated with worse trajectories of pain-related disability during internet-delivered psychological treatment [14], and the protocol of a trial in adolescents with migraine reasons that pain may change after sustained improvements in sleep [15]. An editorial on exercise proposes that daily oral medication or repeated injections serve as bridging therapies towards regular exercise [16]. A common criterion for which treatment comes first, and a statement of the result that would show order to be irrelevant, are missing from these observations.
2. Methods
2.1. Search
This is a narrative review with a stated position. The search is described so that its coverage can be judged, and the logged queries of the final update on 23 September 2026, with record counts, are listed in Supplementary File 1. PubMed and Europe PMC, including its preprint records, were searched from inception to 23 September 2026, without language restriction, combining migraine and headache terms with behavioural, cognitive, mindfulness, acceptance, education, self-management, sleep, insomnia, diet, exercise and lifestyle terms, and separately with CGRP and monoclonal antibody terms. A second search paired terms for treatment order, sequencing, combination, stepped care, delayed start, sequential multiple assignment randomised trials and adaptive interventions with headache terms, to identify comparisons of two treatment orders or timings. A third search was run on the first and last authors of the trials and cohorts the argument rests on, combined with sequencing and mechanism terms, to identify earlier statements of the same idea. Reviews and perspectives published from September 2024 onwards were screened separately for overlap with the present argument, and ClinicalTrials.gov was searched for registered and completed trials. Randomised trials, systematic reviews and guidelines were prioritised, and reference lists of retrieved articles were checked. Table 2 lists the randomised trials read against the classification, and Table 3 those that varied order or timing; the tables are not exhaustive. The trials were selected for relevance to the classification: trials in chronic migraine or medication overuse, trials that combined or sequenced treatments of the two classes, trials whose mechanism or process outcomes bear on the classification, and recent trials of cognitive, mindfulness-based and acceptance-based treatment that reported frequency. The syntheses in Section 4.2 cover the wider literature. Every citation was verified against the primary record, and PMIDs and DOIs appear in the reference list.
2.2. Use of Artificial Intelligence
The concept, the argument, the classification and all scientific decisions in this paper are the author's. Claude (Anthropic) was used, under the author's direction, to search the literature, to draft and edit the text, to verify each reference against the primary record and to write the plotting code for Figure 1. No generative image model was used. The author reviewed and verified all claims, numerical results and references, and takes full responsibility for the content.
3. The Two Classes
3.1. The Distinction
Chronic migraine is defined as headache on at least 15 days per month for more than three months, with the features of migraine on at least eight [17]. Monoclonal antibodies against CGRP or its receptor reduce monthly headache and migraine days in this population in placebo-controlled trials [18,19,20,21] and are recommended in European and international guidance [22,23]; the international recommendations also list atogepant, onabotulinumtoxinA and topiramate for chronic migraine [23]. The ascending pathway is therefore an axis that can be targeted with molecularly specific treatment and measured in headache days.
Migraine involves activation and sensitisation of the trigeminovascular pathway, with CGRP released from trigeminal afferents amplifying transmission [24,25]. Activation of the pathway sensitises central trigeminovascular neurons, which is clinically visible as cutaneous allodynia [26], and allodynia independently predicts an increase in migraine days, a marker of chronification [27]. Alongside this ascending traffic, what the patient does with the signal matters. Catastrophising, fear of pain and pain vigilance are associated with pain-related disability across clinical pain conditions [28], as the fear-avoidance model proposes [29], and in migraine the Tampa Scale for Kinesiophobia correlates moderately with headache impact and catastrophising [30]. Treatments addressing that side of the problem have a long record in headache medicine [7,31], and a systematic review found low-strength evidence that several of them may reduce attack frequency and that education may improve disability [6]. Bayesian accounts describe the interpretive side as a precision-weighted prior against which ascending evidence is compared, and chronic pain as a state in which that prior comes to dominate [32]. The argument uses that formulation as a convenient statement of the distinction. The same two classes can also be described in terms of afferent input and its cortical appraisal.
Two classes of intervention follow (Fig. 1). Drive-lowering interventions are proposed to reduce the generation or transmission of nociceptive signals, including through medication use, sleep and lipid mediators. Interpretation-directed interventions are proposed to change appraisal, attention, expectation and the behavioural response to a signal. Expectation-induced placebo analgesia reduces nociceptive processing in the spinal cord [33], and behavioural treatments are held to modulate nociplastic mechanisms in medication-overuse headache [8], so interpretation-directed interventions may also lower drive. The proposal therefore expects smaller frequency effects from that route while drive remains high, and does not require them to be absent. Table 1 assigns the commonly used non-pharmacological treatments to the two classes.
Each assignment rests on a mechanism stated in a cited source (Table 1), because classifying interventions by their results would make the framework unfalsifiable. The rule used is: an intervention is drive-lowering if its proposed mechanism is a change in afferent input, in its peripheral generation, or in a physiological state that generates it; it is interpretation-directed if its proposed mechanism is a change in appraisal, attention, expectation or behavioural response. Packages are coded by component. A package counts as interpretation-directed if all of its components are, and a package with components on both sides is classed as mixed and treated as uninformative for the order prediction. A drive-lowering component counts as having lowered drive when its mediator moved, for example acute-medication days after withdrawal or sleep measures after insomnia treatment. The same rule splits what is called education. Advice whose aim is withdrawal of overused medication acts through the drive it removes and belongs with withdrawal. Education and self-management programmes aimed at beliefs, expectations and self-efficacy are interpretation-directed. For fixed-dose conditioning, the avoidance mechanism was proposed after a null mechanistic result [34], and conditioning is classed as mixed. Acupuncture, manual therapy, non-invasive neuromodulation and nutraceuticals are outside the scope of Table 1, because the sources reviewed describe their proposed mechanisms across both classes without separating components.
The readings in Table 2 follow four further rules, which the author specified after the trials were known. First, a drive-side component whose mediator, measured separately from the frequency outcome, did not move is disregarded in coding the package. Second, drive at randomisation is high in chronic migraine and in medication overuse unless a drive-lowering treatment whose mediator moved was in place, lowered when such a treatment was in place, and unclassified in episodic migraine without one; a sample counts as high drive when most participants have chronic migraine or medication overuse. Third, drive-lowering components are expected to reduce frequency in any state, including a drive-lowering component of a mixed package when its mediator moved; interpretation-directed components are expected to change monthly migraine days by less than 1.5 days under high drive and to reduce them once drive has been lowered; other mixed packages are expected to reduce frequency once drive has been lowered; and process measures are expected to improve in any state. Interpretation-directed treatments and other mixed packages carry no frequency prediction when drive is unclassified, and other mixed packages carry none under high drive. Fourth, a result fits or does not fit only when it is decisive by these margins, and a non-significant result from a small trial or a secondary outcome is inconclusive; a mixed package whose frequency result fits is recorded as compatible, because it does not isolate the interpretation-directed component.

Table 2.
Randomised trials read against the classification with the rules in Section 3.1. Column 3 gives the drive-lowering treatment in place when the randomised intervention was given, and column 4 the class of the randomised component; a dash means that the item was not stated in the sources consulted.
| Trial | Population | Drive-lowering treatment in place | Randomised contrast (class) | Frequency outcome | Impact and process outcomes | Reading |
|---|---|---|---|---|---|---|
| RESOLUTION [35,36] | 608 adults with chronic migraine and medication-overuse headache, opioid overuse excluded | brief education about medication overuse in both arms | eptinezumab vs placebo (drive-lowering) | monthly migraine days weeks 1–4: −6.9 vs −3.7 (difference −3.2, 95% CI −4.2 to −2.2); placebo arm caught up after switching at week 12 | superior on all key secondary endpoints through week 12 | fits |
| Ramsden et al. [45] | 182 adults with migraine on 5–20 days per month (mean 16.3 headache days), 67% chronic migraine, 56% acute-drug overuse | usual care continued, preventive changes allowed | n-3 raised and n-6 lowered vs control diet (drive-lowering) | −4.0 headache days per month (−5.2 to −2.7), a secondary outcome | 17-hydroxydocosahexaenoic acid rose; HIT-6 −1.6 (−4.2 to 1.0), not significant | fits |
| Calhoun and Ford [12] | 43 women with transformed migraine | usual medical care | behavioural sleep instructions vs placebo instructions (drive-lowering) | reduced against placebo instructions at 6 weeks | reversion to episodic migraine more frequent | fits |
| Smitherman et al. [40,41] | 31 adults with chronic migraine and comorbid insomnia, medication overuse excluded | stable usual medication | cognitive-behavioural therapy for insomnia vs control (drive-lowering) | 48.9% vs 25.0% reduction at 6-week follow-up (odds ratio 0.40, 0.17 to 0.91; not significant after correction); −6.2 headache days per month in the completer analysis pooled with [12] (95% credible interval −9.7 to −2.7) | sleep time, sleep efficiency and insomnia severity improved | inconclusive; direction as predicted |
| Spierings et al. [44] | 79 adults with migraine and primary insomnia | – | eszopiclone vs placebo for 6 weeks (drive-lowering) | no difference | total sleep time endpoint not met; fewer night-time awakenings | uninformative; primary sleep mediator did not move |
| Pijpers et al. [39] | 179 adults with medication-overuse headache, concealed within a placebo-controlled trial of botulinum toxin | withdrawal in both arms | maximal vs minimal nurse-led behavioural support (mixed) | monthly migraine days −6.75 vs −6.22; no difference at any assessment to 48 weeks | acute-medication days −2.23 at week 24 (−3.76 to −0.70) | inconclusive; migraine days reported without a test or interval |
| CHESS [1,47] | 727 of 736 randomised adults with chronic headache, those with migraine, 56% with medication overuse | advice on prevention and overuse given; drug use unchanged | education and self-management vs usual care with relaxation material (interpretation-directed in effect) | 0.9 headache days at 12 months (−0.29 to 2.05); 1.5 more at 4 months (0.48 to 2.56) | pain self-efficacy improved at 4 and 12 months; HIT-6 −0.3 at 12 months (−1.23 to 0.67) | inconclusive for frequency (secondary outcome); self-efficacy as predicted; impact unchanged |
| Thorn et al. [48] | 34 treated and 11 wait-listed adults with chronic headache | – | cognitive-behavioural treatment targeting catastrophising vs wait-list (interpretation-directed) | no overall difference | catastrophising and anxiety fell; self-efficacy rose | inconclusive for frequency; process as predicted |
| Seng et al. [50,51] | 60 adults with 6–30 headache days per month (mean 16.0), 52% chronic migraine | treatment as usual | mindfulness-based cognitive therapy vs wait-list or usual care (interpretation-directed) | no difference in headache days, a secondary outcome | Headache Disability Inventory reduced overall (MIDAS not significant after correction); chronic migraine moderated the effect on severe disability | inconclusive for frequency (secondary outcome in a pilot); disability effect smaller in chronic migraine |
| Klan et al. [52] | 121 adults with mostly episodic migraine | none; prophylactic medication and medication overuse excluded | cognitive-behavioural programme with relaxation vs relaxation vs waiting list (mixed) | no between-group difference | self-efficacy improved with both treatments against waiting list; disability did not differ | uninformative; both treatments mixed |
| Wells et al. [56] | 89 adults with 4–20 migraine days per month (mean 7.3), medication overuse excluded | stable preventive treatment allowed (40% vs 71%) | mindfulness-based stress reduction with yoga vs headache education (mixed vs interpretation-directed) | no difference (p = 0.50) | disability, quality of life and self-efficacy improved | uninformative for frequency; impact compatible |
| Fox et al. [49] | 55 adults analysed, at least 4 migraine days per month | – | online cognitive restructuring of catastrophising vs active control (interpretation-directed) | fell within the intervention arm; no between-group test reported | catastrophising fell; its fall raised the adjusted explained variance in disability change from 7% to 24% | uninformative for frequency; process as predicted |
| Powers et al. [57], with [58] | 135 adolescents with chronic migraine | amitriptyline in both arms; it did not differ from placebo in a later paediatric trial | cognitive-behavioural therapy with biofeedback-assisted relaxation vs headache education (mixed) | −11.5 vs −6.8 headache days (difference 4.7, 1.7 to 7.7) | disability 14.1 points lower (3.3 to 24.9) | uninformative by the rules (mixed package under high drive); does not fit if read as interpretation-directed |
| MIND-CM [2] | 177 adults with chronic migraine and medication-overuse headache | withdrawal and tailored prophylaxis in both arms; intakes per headache day fell in both arms | mindfulness addressing medication use added vs treatment as usual (mixed) | 78.4% vs 48.3% with at least 50% reduction at 12 months | migraine-specific quality of life and MIDAS better at 12 months; HIT-6 and mindful awareness did not differ; intakes per headache day −23% vs −6% | compatible; does not isolate the component |
| Holroyd et al. [63] | 232 adults with frequent episodic migraine despite optimised acute treatment | none effective; at least three disabling migraines per 30 days on optimised acute treatment | β-blocker, behavioural migraine management, both, or placebo (drug drive-lowering; behavioural package mixed) | combination only (−3.3 vs −2.1 migraines per 30 days) | quality of life improved with behavioural management alone and most with the combination | does not fit for the β-blocker alone; combination compatible |
| Golovacheva et al. [43] | 96 adults with chronic migraine and chronic insomnia | preventive and acute pharmacotherapy with lifestyle and sleep-hygiene advice in both arms | cognitive-behavioural therapy for pain and insomnia added vs standard care (mixed) | at least 50% reduction in 81.5% vs 33% at 18 months; not significant at 3 months | insomnia severity improved | compatible; does not isolate the component |
| Varkey et al. [69] | adults with episodic migraine | not applicable; topiramate was one of the randomised arms | exercise vs relaxation vs topiramate (mixed, mixed, drive-lowering) | similar reductions, about one attack per month | – | uninformative |
| Krøll et al. [34,70] | adults with migraine, tension-type headache and neck pain | – | aerobic exercise vs usual activity (mixed; pain-modulation measures did not move) | migraine burden reduced | no consistent change in pain sensitivity measures | uninformative; mechanism points to avoidance |
| Seminowicz et al. [53] | 98 adults with episodic migraine | – | enhanced mindfulness-based stress reduction vs stress management for headache (mixed vs interpretation-directed) | headache days 7.8 to 4.6 vs 7.7 to 6.0 at 20 weeks (p = 0.04); no difference at 52 weeks | disability improved more at 20 weeks | uninformative (drive unclassified) |
| Simshäuser et al. 2022 [54] | 54 adults with episodic migraine, about 6 migraine days per month | stable prophylaxis allowed (15% vs 7%); chronic migraine and medication overuse excluded | migraine-specific mindfulness-based cognitive therapy vs waiting list (interpretation-directed) | headache frequency reduced (p = 0.04) | headache-related impairment unchanged; catastrophising reduced | uninformative for frequency (drive unclassified); process as predicted |
| Simshäuser et al. 2020 [55] | 62 adults with migraine | – | mindfulness-based stress reduction vs relaxation with psychoeducation (mixed vs mixed) | no difference in migraine days | pain self-efficacy improved more | uninformative |
| Grazzi et al. 2021 [62] | 35 adults with high-frequency episodic migraine | prophylaxis stable for 3 months in both arms; mediator not documented | acceptance and commitment therapy added vs treatment as usual (interpretation-directed) | −3.3 vs +0.7 headache days at 3 months (difference 4, 1.2 to 6.8); no difference at 6 and 12 months | headache impact and pain acceptance changed in favour of treatment as usual | does not fit for process; frequency uninformative (drive unclassified) |
3.2. Why Order Should Follow
If both classes simply added their effects, order would be irrelevant. An intervention directed at interpretation makes the patient's estimate of their bodily state more revisable. The direction of that revision is set by the evidence available at the time. While afferent drive remains high, the available evidence supports the pain interpretation, and a more revisable estimate returns to it. Lowering drive first provides an alternative state for the estimate to move to, and loosening the expectation then changes what the patient experiences as well as how they cope with it.
The model predicts non-additivity and asymmetry, since the benefit of combining the classes should depend on the drive-lowering component coming first or alongside. Its frequency predictions for high and lowered drive are those given in Section 3.1, and for process measures such as self-efficacy, catastrophising and acceptance it predicts improvement in any drive state. A stronger form of the model would predict that disability and headache impact also improve under high drive. CHESS and the chronic-migraine subgroup of a trial of mindfulness-based cognitive therapy do not support that form (Section 4.2), and Section 6 treats impact as drive-dependent, a specification that follows the results that prompted it and is stated as a prediction for future trials.
4. The Evidence Read Against the Classification
The trials reviewed here were not designed to test the proposal, and reading them against it is post hoc. Section 6 gives the prospective tests. Table 2 lists 22 randomised trials with the drive-lowering treatment in place when each randomised intervention was given, the class of the randomised component under the rule in Section 3.1, and a reading of each result under the rules given there. Three fit, two do not, two are compatible without isolating the component in question, five are inconclusive and ten are uninformative for the proposal; if the Powers trial is read as interpretation-directed, three do not fit. All three trials that fit test the premise that drive-lowering treatment reduces frequency. No trial in Table 2 tests the prediction for interpretation-directed treatment under high drive decisively, and CHESS comes closest (Section 4.2). Table 3 lists the studies that varied order or timing. Most psychological packages tested in migraine combine components from both classes, typically relaxation, biofeedback or medication-use training alongside cognitive or mindfulness components, so few trials isolate an interpretation-directed component. That mixture is one candidate explanation for the heterogeneity that systematic reviews report [3,6].
Table 3.
Studies that varied the order or timing of two treatments in headache.
| Study | Population | Treatments and orders | Result | Class of the treatments | Reading |
|---|---|---|---|---|---|
| Knapp 1982 [65] | 16 patients with migraine | temporal-artery vasoconstriction biofeedback and cognitive coping training, alone or in either serial order; allocation method not given in the abstract | all groups improved; no group differences at one year | biofeedback aimed at the vasculature, classed as mixed; cognitive coping interpretation-directed | too small to inform |
| Kropp et al. 1997 [66] | 38 patients with migraine without aura | blood-volume-pulse biofeedback then cognitive-behavioural therapy, or the reverse | biofeedback first significantly better | mixed, then interpretation-directed | uninformative; readiness explanation |
| Thorn et al. 2007 [48] | adults with chronic headache | two cognitive-behavioural modules in either order | order unrelated to gains | both interpretation-directed | compatible; no order effect predicted |
| Carlsen et al. 2020 [38] | 120 adults with medication-overuse headache | withdrawal with preventive treatment from the start, preventive treatment alone, or withdrawal with optional preventive treatment after 2 months | headache days −12.3, −9.9 and −8.5 (p = 0.20); reversion to episodic headache 74%, 60% and 42% | both drive-lowering | compatible for the primary outcome; reversion to episodic headache and cure of overuse favour starting together, other secondary outcomes did not differ |
| RESOLUTION 24-week results [36] | 608 adults with chronic migraine and medication-overuse headache | eptinezumab from week 0 or from week 12, education in both arms | delayed-start arm reached similar improvement | both drive-lowering | compatible |
| ISPY [15] | 224 adolescents with migraine and insomnia | cognitive-behavioural therapy for insomnia or sleep education for 6 weeks, then cognitive-behavioural therapy for pain for 6 weeks in all | completed May 2026; results not posted by 23 September 2026 | insomnia treatment or sleep education, then interpretation-directed | prediction stated in Section 6 |
4.1. Drive-Lowering Treatments in High-Drive Populations
CGRP-pathway antibodies reduce monthly migraine days in chronic migraine [18,19,20,21], and a 2026 trial tested one in chronic migraine with medication overuse. RESOLUTION randomised 608 adults with chronic migraine and medication-overuse headache, all of whom received a brief educational intervention about medication overuse, to eptinezumab or placebo. Monthly migraine days in weeks 1–4 fell by 6.9 against 3.7 (difference −3.2, 95% CI −4.2 to −2.2), and eptinezumab was superior on all key secondary endpoints through week 12 [35]. After week 12, when all participants received eptinezumab, those who had started on placebo reached similar levels of improvement by week 24 [36]. The education given to both arms was advice about medication overuse, which the rule places with withdrawal, so the trial randomised one drive-lowering treatment against a background of another.
Withdrawal of overused acute medication is a behavioural intervention. The European Academy of Neurology guideline makes education and counselling the first step in medication-overuse headache, recommends withdrawal with preventive treatment when education fails, and recommends slow tapering for opioids, barbiturates and tranquillisers [37]. Of the trials in Table 2, two bear on how withdrawal combines with other treatment. In 120 patients with medication-overuse headache, withdrawal with preventive treatment from the start, preventive treatment without withdrawal, and withdrawal with optional preventive treatment after two months reduced headache days by 12.3, 9.9 and 8.5 per month (p = 0.20); reversion to episodic headache (74%, 60% and 42%) and cure of medication overuse favoured starting both together [38]. In 179 patients undergoing withdrawal, a maximal nurse-led behavioural programme of education, motivational interviewing and value-based activity planning reduced acute-medication days at week 24 more than minimal contact (mean difference −2.23, 95% CI −3.76 to −0.70), without a difference in the change in monthly migraine days (−6.75 against −6.22), and the authors report no difference in migraine days at any assessment to 48 weeks [39]. Under the classification the programme combines drive-side support for withdrawal with an interpretation-directed component. Withdrawal had lowered drive, so the proposal expects the added package to reduce migraine days further. Migraine days were reported without a test or interval, so by the fourth reading rule the result is inconclusive, with point estimates at 36 and 48 weeks that run against the proposal.
Behavioural treatment of comorbid insomnia points the same way as the antibodies, on weaker evidence. In 43 women with transformed migraine, behavioural sleep instructions reduced headache frequency against placebo instructions over six weeks, and reversion to episodic migraine was more frequent [12]. A randomised pilot in 31 adults with chronic migraine and comorbid insomnia found reductions in headache frequency with both cognitive-behavioural therapy for insomnia and a control intervention immediately after treatment (26.9% and 36.2%), and a larger reduction with insomnia treatment at six-week follow-up (48.9% and 25.0%; odds ratio 0.40, 95% CI 0.17 to 0.91, p = 0.028, not significant after correction for two primary endpoints); insomnia treatment also increased actigraphic sleep time and sleep efficiency, so its proposed mediator moved [40]. Combining the two trials in a sequential Bayesian analysis gave a reduction of 6.2 headache days per month more than control among completers (95% credible interval −9.7 to −2.7) [41]. A 2026 systematic review found that digital cognitive-behavioural therapy for insomnia reduced headache days, while evidence for standard delivery was mixed [42]. In 96 patients with chronic migraine and chronic insomnia, a programme combining cognitive-behavioural therapy for pain and for insomnia with standard care, which comprised preventive and acute pharmacotherapy with lifestyle and sleep-hygiene advice, led to more patients with at least a 50% reduction in headache frequency at 18 months than standard care alone (81.5% against 33%), a difference that was not significant at three months [43]. A hypnotic that did not meet its primary endpoint for total sleep time did not change headache frequency [44], which does not test the pharmacological route to the same mediator.
In a three-arm controlled trial of 182 adults with migraine on 5–20 days per month, 67% of whom met criteria for chronic migraine and 56% for acute-drug overuse, and who continued usual care with changes in preventive drugs allowed, a diet raising eicosapentaenoic and docosahexaenoic acid while lowering linoleic acid reduced headache days by 4.0 per month against the control diet (95% CI −5.2 to −2.7) and headache hours per day by 1.7 (−2.5 to −0.9) [45]. Headache frequency was a secondary outcome. The co-primary endpoints were the antinociceptive mediator 17-hydroxydocosahexaenoic acid, which rose, and HIT-6, whose difference of −1.6 (95% CI −4.2 to 1.0) was not statistically significant and has a point estimate at the between-group minimally important difference of 1.5 points [46]. The diets altered several nociceptive oxylipins and did not change circulating CGRP or prostaglandin E2 [45], so the drive-lowering assignment rests on lipid mediators of nociception. Participants received foods supplying two thirds of their daily energy for 16 weeks, and feasibility outside a trial was not addressed in the trial report.
4.2. Interpretation-Directed and Mixed Treatment Without a Documented Drive-Lowering Step
The two 2023 trials in the Introduction differ on the drive-lowering treatment in place. In CHESS, 32% of the 727 participants with migraine had used prophylactic medication, 56% had medication-overuse headache and three participants in the whole trial received a CGRP-pathway antibody. The nurse component gave advice on preventive medication and on avoiding medication overuse, and yet the numbers using acute and prophylactic drugs did not change over the trial or differ between arms, and the proportions using acute medication on at least 10 or at least 15 days in the preceding 28 days did not differ between arms at any follow-up, which the authors take to indicate no effect on medication overuse [1]. By the first reading rule in Section 3.1 the drive-side component is disregarded, and the randomised contrast was in effect an interpretation-directed programme given under high drive. The programme report gives further results. Pain self-efficacy improved at 4 and 12 months. At 4 months HIT-6 favoured the programme (−1.0, 95% CI −1.91 to −0.006) while the programme group reported 1.5 more headache days in the preceding 28 days (0.48 to 2.56), and at 12 months the confidence interval for HIT-6 excluded a worthwhile benefit [47]. The confidence interval for headache days at 12 months excludes a reduction of 1.5 days, but headache days were a secondary outcome and the interval extends to an increase of 2.05 days, so by the fourth reading rule the frequency result is inconclusive; self-efficacy improved as predicted. The absence of an improvement in impact at 12 months counts against the stronger form of the model in Section 3.2.
Other trials show the same pattern for process measures. In a small trial of cognitive-behavioural treatment targeting catastrophising in chronic headache, with 34 participants treated and 11 wait-listed, catastrophising and anxiety fell and self-efficacy rose against the wait-list, without an overall difference in headache frequency or intensity, a frequency result that is inconclusive at that size [48]. In a proof-of-concept trial analysing 55 adults with at least four migraine days per month, an online cognitive-behavioural intervention reduced catastrophising at the end of treatment, and in a regression across both arms, adjusted for change in attack frequency and depressive symptoms, adding the fall in catastrophising raised the adjusted explained variance in the fall in disability from 7% to 24% [49]. Mindfulness-based cognitive therapy for migraine reduced headache disability against wait-list or usual care in 60 adults averaging 16 headache days per month, 52% with chronic migraine, and diary-recorded headache days, a secondary outcome of this pilot trial, did not differ between groups [50]. In a planned secondary analysis, chronic migraine moderated the effect on severe disability (p = 0.013), with larger benefit in episodic migraine, and the reduction on the Headache Disability Inventory was significant in episodic (p = 0.011) and not in chronic migraine (p = 0.268) [51]. A three-armed trial in adults with mostly episodic migraine, with prophylactic medication and medication overuse excluded, found that a migraine-specific cognitive-behavioural programme that included relaxation training and relaxation alone both improved self-efficacy against a waiting list, without between-group differences in headache days or disability [52].
Mindfulness-based trials outside chronic migraine show that frequency can fall with these treatments. Enhanced mindfulness-based stress reduction reduced headache days at 20 weeks more than stress management for headache in 98 adults with episodic migraine (from 7.8 to 4.6 against 7.7 to 6.0 days; p = 0.04), without a difference at 52 weeks [53]. In 54 patients with migraine, a migraine-specific adaptation of mindfulness-based cognitive therapy reduced headache frequency against a waiting list (p = 0.04) without improving headache-related impairment, and reduced catastrophising [54]; in 62 patients, mindfulness-based stress reduction did not reduce migraine days more than relaxation with psychoeducation and improved pain self-efficacy [55]. Under the rules in Section 3.1 these trials carry no frequency prediction, because drive in these populations is unclassified.
In a randomised trial of 89 adults with 4–20 migraine days per month (mean 7.3) and without medication overuse, mindfulness-based stress reduction, which combines mindfulness with yoga, was compared with headache education. Migraine days fell in both groups at 12 weeks without a difference between them (−1.6, 95% CI −2.5 to −0.7, against −2.0, −2.9 to −1.1; p = 0.50), while mindfulness-based stress reduction improved disability (between-group difference 5.92, 95% CI 2.8 to 9.0), quality of life (5.1, 1.2 to 8.9) and self-efficacy across the 12-, 24- and 36-week follow-ups [56]. The mindfulness arm included yoga, which the rule classes as mixed, the comparator was education, and 40% of the mindfulness arm and 71% of the education arm were taking prophylaxis at baseline, so the trial does not test the frequency prediction; its impact results come from a predominantly episodic population.
The strongest result against the proposal among the trials reviewed comes from adolescents. In 135 young people aged 10–17 years with chronic migraine, all of whom started amitriptyline, cognitive-behavioural therapy reduced headache days at 20 weeks by 11.5 against 6.8 with headache education of equal therapist time (difference 4.7, 95% CI 1.7 to 7.7), and reduced disability by 14.1 points more (3.3 to 24.9) [57]. In a later placebo-controlled trial in children and adolescents with migraine, not restricted to chronic migraine, amitriptyline did not differ from placebo in headache frequency or disability [58]. The drive-lowering step in place is therefore doubtful, and frequency fell with a psychological package given from the start. The package included biofeedback-assisted relaxation, which the classification marks as mixed, and under the rules in Section 3.1 a mixed package given under high drive carries no frequency prediction. If the effect came from the cognitive components, the result does not fit the proposal, and the tally in Section 4 is given both ways.
Syntheses point in different directions on frequency. A meta-analysis of acceptance-based interventions found an effect on disability (standardised mean difference −0.38, 95% CI −0.56 to −0.20) and no significant effect on headache frequency (−0.16, −0.37 to 0.05) or medication use [59], a pattern compatible with the classification, although the drive state of the pooled trials is not reported. A meta-analysis of 14 trials of mindfulness-based interventions in 1027 adults found a small reduction in attack frequency (standardised mean difference 0.33, 95% CI 0.11 to 0.54), improvements in quality of life (0.24, 0.08 to 0.40) and pain catastrophising (0.57, 0.35 to 0.80), and no significant effect on activity-related disability (0.18, −0.01 to 0.38) or on analgesic and triptan use [60]. Both meta-analyses include mindfulness-based trials, and they disagree on frequency. The systematic review of 50 trials in adults rated as low-strength the evidence that cognitive-behavioural therapy, relaxation training and mindfulness-based therapies may each reduce attack frequency, and, on equally low-strength evidence, that education alone may improve disability; in children and adolescents, cognitive-behavioural therapy with biofeedback and relaxation training may reduce attack frequency and disability more than education alone [6]. If the frequency effects in these syntheses arose in patients whose drive had not been lowered, they count against the proposal. The systematic review of 50 trials does not report the preventive treatment in place, the meta-analysis abstracts do not either, and many of the pooled packages are mixed. In the mindfulness meta-analysis the frequency effect was not accompanied by a change in analgesic or triptan use, so it did not run through medication use, which strengthens it as evidence against the proposal if the pooled patients had high drive [60]. An individual-patient-data analysis by drive state would decide the question, and Prediction 4 describes the analogue for new add-on trials.
4.3. Interpretation-Directed and Mixed Treatment with Drive-Lowering Treatment in Place
In MIND-CM every participant underwent a 5–8-day inpatient or day-hospital withdrawal, received education on medication use and lifestyle, and was prescribed tailored prophylaxis by the end of withdrawal; randomisation took place on the second day of withdrawal, and six weekly mindfulness sessions were added in one arm [2]. In per-protocol analyses of secondary outcomes, migraine-specific quality of life and the Migraine Disability Assessment (MIDAS) favoured mindfulness at 12 months, HIT-6 scores and mindful awareness did not differ between arms, more patients in the mindfulness arm reached a clinically meaningful reduction in HIT-6, and intakes per headache day fell by about 23% with mindfulness against 6% with treatment as usual [2]. The mindfulness protocol explicitly addressed the "pain-pill automatism", so under the rule in Section 3.1 the added component also acted on medication use, which is drive-side. The trial is compatible with the proposal for a mixed package given with drive lowered and cannot isolate the interpretation-directed component. A recent review reads it as showing an additive effect of mindfulness [8]. Separating an additive from a conditional effect would need an arm receiving mindfulness without withdrawal and prophylaxis. In an earlier non-randomised study from the same group, mindfulness alone after withdrawal and pharmacological prophylaxis after withdrawal were followed by similar reductions in headache frequency, with HIT-6 improving only in the prophylaxis group [61]. In a randomised pilot trial in 35 patients with high-frequency episodic migraine on prophylaxis that had been stable for three months, adding acceptance and commitment therapy reduced headache days at three months (−3.3 against +0.7; difference 4, 95% CI 1.2 to 6.8) and medication intake, without differences at 6 and 12 months, and headache impact and pain acceptance changed in favour of treatment as usual [62]. The frequency effect occurred with a drive-lowering treatment in place whose mediator was not documented, and the change in acceptance, the process the therapy targets, does not fit the process prediction.
A factorial trial in frequent episodic migraine bears on both classes. Holroyd et al. randomised 232 adults who continued to have at least three disabling migraines per 30 days (mean 5.5) during a run-in of optimised acute treatment, with probable medication overuse excluded, to added β-blocker, added behavioural migraine management, both, or placebo [63]. At month 10, neither component alone improved migraine frequency beyond optimised acute treatment alone (β-blocker −2.1 migraines per 30 days, 95% CI −2.2 to −1.9; behavioural management −2.2, −2.4 to −2.0; optimised acute treatment alone −2.1, −2.2 to −1.9), and the combination did (−3.3, −3.5 to −3.2). Behavioural management alone improved migraine-specific quality of life beyond optimised acute treatment alone or with β-blocker, and the combination improved it most [63]. Behavioural migraine management combines relaxation, thermal biofeedback, stress management and trigger management [63], and in the same trial it reduced catastrophising more than drug therapy alone [64]. Under the classification it is mixed. The combination-only effect on frequency is compatible with an interaction between the two kinds of treatment, and the effect of behavioural management on quality of life without a change in frequency is compatible with the process route; the classification makes no frequency prediction for this episodic population. The failure of the β-blocker alone to reduce frequency does not fit the premise that drive-lowering treatment reduces frequency. Both components started together, so the trial does not address order.
4.4. Studies that Varied Order or Timing
Table 3 lists six studies that varied the order or timing of two treatments in headache, one of which is awaiting results. In 16 patients, Knapp gave biofeedback training in vasoconstriction of the temporal arteries, a treatment aimed at the extracranial vasculature, and cognitive coping training, each alone or in one of the two serial orders; all groups improved and did not differ at one year, with four patients per group and the method of allocation not given in the abstract [65]. Kropp and colleagues gave 38 patients with migraine without aura blood-volume-pulse biofeedback followed by cognitive-behavioural therapy, or the same two treatments in reverse order; the first sequence did significantly better, which the authors attributed to biofeedback helping patients to recognise the influence of thoughts and emotions on bodily reactions [66]. In a trial of cognitive-behavioural treatment for catastrophising in chronic headache, the order of two treatment modules, cognitive restructuring and cognitive-behavioural coping, was unrelated to gains [48]. The timing of preventive medication around withdrawal [38] and a delayed antibody start with education held constant [36] are described in Section 4.1.
These studies bear on the proposal unevenly. Biofeedback is mixed, so the Kropp result is recorded as uninformative for the proposal. Its explanation, psychological readiness, is the timing-in-general alternative that Prediction 3 is designed to separate. Knapp's vasoconstriction biofeedback was aimed at the vasculature, but the rule classes biofeedback as mixed, and with four patients per group the study cannot inform the question. Thorn varied order within the interpretation-directed class, where the proposal predicts no order effect. Carlsen and RESOLUTION varied timing within the drive-lowering class, where the proposal also predicts no order effect. The delayed-start arm of RESOLUTION caught up, and in Carlsen the primary outcome did not differ while reversion to episodic headache favoured starting both treatments together. A randomised comparison of the same drive-lowering and interpretation-directed treatments given in both orders, at adequate size, was not found in the search.
The Intervention for Sleep and Pain in Youth (ISPY) trial comes closest to the adjacent claim that a drive-lowering behavioural treatment given first improves the response to an interpretation-directed one. It randomised adolescents aged 11–17 years with migraine, headache on at least six days per month and comorbid insomnia to six weeks of internet-delivered cognitive-behavioural therapy for insomnia or sleep education, after which all received six weeks of internet-delivered cognitive-behavioural therapy for pain [15]; it enrolled 224 participants and was completed in May 2026, and no results had been posted or published by 23 September 2026 (ClinicalTrials.gov NCT04936321). Its primary outcome after the second phase is activity limitation, with headache frequency from 14-day diaries among the secondary outcomes. A numerical prediction for the trial is stated in Section 6 before its results are known.
4.5. Exercise and Graded Activity
Exercise reduces migraine frequency in populations not selected for prior control of attack frequency. A network meta-analysis of 21 trials and 1195 patients ranked strength training first (mean difference −3.55 monthly migraine days, 95% CI −6.15 to −0.95), followed by high-intensity aerobic exercise (−3.13, −5.28 to −0.97) and moderate-intensity aerobic exercise (−2.18, −3.25 to −1.11), with topiramate at −0.98 (−4.16 to 2.20) and amitriptyline at 3.82 (−1.03 to 8.68); the confidence intervals for both drugs include no effect, so the comparison ranks the exercise interventions above them without establishing superiority [67]. A later network meta-analysis of 28 studies and 1501 participants ranked yoga and high-intensity aerobic exercise highest for frequency, and rated the evidence as of very low quality [68]. In a randomised trial in episodic migraine, exercise, relaxation and topiramate produced similar reductions of about one attack per month with no difference between groups [69].
Krøll et al. randomised persons with migraine and coexisting tension-type headache and neck pain to three months of aerobic exercise or usual activity and measured pericranial tenderness, pressure pain thresholds, suprathreshold sensitivity and temporal summation; aerobic exercise produced no consistent change in any of them, and the authors concluded that the reduction in migraine burden found in the primary report of the same trial [70] is more plausibly explained by altered avoidance behaviour than by altered pain modulation [34]. Exercise-induced hypoalgesia typically follows a single bout of exercise in pain-free people, and is more variable and more often impaired in chronic pain populations [71]. Fixed-dose conditioning is classed as mixed because the cited sources propose both mechanisms for it (Section 3.1), so the Varkey and Krøll trials are uninformative for the proposal. An editorial on exercise prescription in migraine proposes preventive drugs as a bridge to regular exercise, with time-contingent pacing for patients new to exercise and supervised graded exposure for those with kinesiophobia, on the rationale of sustainable lifestyle change and greater self-efficacy, health locus of control and patient agency [16].
The same physical activity can be delivered with an interpretation-directed target. Graded activity is an operant approach in which activity is increased by time-contingent progression set in advance [72,73], so that progression does not wait for symptoms to settle and the rule that activity stops when symptoms begin is broken. It targets the avoidance behaviour that the fear-avoidance model describes [29], and it is distinct from fear-based graded exposure [74]. Patients with migraine rate particular exercises as fear-inducing in proportion to their fear-avoidance beliefs and inversely to their activity level [75]. A multimodal programme of therapeutic education and exercise has been proposed for migraine, grounded in the association of kinesiophobia, catastrophising and low self-efficacy with migraine-related disability, with fear of movement, avoidance behaviour and self-efficacy as its targets [76].
On the classification, graded activity is interpretation-directed and belongs in the second step. No randomised trial of graded activity in migraine was identified. In persistent low back pain, a systematic review of 15 trials and 1654 patients found graded activity superior to minimal or no treatment by small margins on a 0–100 scale (pain −6.2, 95% CI −9.4 to −3.0; disability −6.5, −10.1 to −3.0 in the short term), and no significant difference between graded activity and another form of exercise, or between graded activity and graded exposure [74]. Exposure in vivo outperformed pain-contingent usual care in complex regional pain syndrome type 1 [77], which shows that exposure-based treatment can work outside back pain. Graded activity is of interest here because it can be matched with symptom-contingent conditioning on modality and planned dose while differing in its progression rule, which separates the interpretation-directed component of physical activity from its physiological one. Prediction 5 states the test.
5. Clinical Implications
For a headache clinician, the classification mainly changes what each step can be expected to achieve. Table 4 sets out the steps. The first step lowers drive. It includes screening for medication overuse and structured withdrawal after education and counselling, with slow tapering for opioids, barbiturates and tranquillisers [37]; starting or optimising preventive treatment, with CGRP-pathway antibodies, atogepant, onabotulinumtoxinA and topiramate among the options recommended for chronic migraine [23]; and screening for insomnia, with behavioural treatment where it is present, including digital delivery [13,42]. Behavioural medicine belongs to this step as well, since education and counselling for medication overuse, support during withdrawal and behavioural treatment of insomnia are behavioural interventions that lower drive.
Whether drive has fallen can be judged in clinic from diaries and medication counts, as acute-medication days below the overuse thresholds of the classification [17], fewer migraine days after an adequate trial of preventive treatment, and, where insomnia was treated, lower insomnia severity. The proposal expects interpretation-directed treatment to reduce attack frequency mainly once these indices have moved, and expects improvements in self-efficacy and coping earlier. Patients can be told which outcomes each step is likely to change.
Interpretation-directed treatment should be offered alongside the first step when disability or distress is high, when the patient prefers it, when preventive treatment is unavailable, not tolerated or declined, and in pregnancy, for which international recommendations suggest non-pharmacological treatments or peripheral nerve blocks as first-line options [23] and the European guideline suggests avoiding CGRP-pathway antibodies [22]. Prescription and reimbursement rules for CGRP-pathway antibodies differ between countries [22], and where they delay access, the other preventive options and the behavioural drive-lowering treatments carry the first step. Sleep restriction, a component of behavioural treatment of insomnia, is associated with increased daytime sleepiness and reduced vigilance during treatment [78], which matters for patients who drive or work in safety-critical roles. The dietary intervention with the best trial evidence supplied two thirds of daily food energy [45], and the trial did not test delivery in routine care.
6. Research Agenda: Predictions that Could Refute the Rule
Each prediction below names the design, the analysis and the result that counts against the proposal. Monthly migraine days are the primary frequency outcome throughout, with moderate-to-severe headache days as a secondary outcome to separate a change in attacks from a change in reporting. Medication overuse is withdrawn identically before baseline or excluded, and acute-medication days are recorded as a mediator. Where an interval meets both a supporting and a refuting criterion, the result counts against the proposal.
Prediction 1. Conditional efficacy. Adults with chronic migraine start a CGRP-pathway antibody or placebo, continued throughout. Where placebo is unacceptable, an immediate and a 24-week-delayed antibody start can replace it. At week 12 participants are randomised again to a standardised interpretation-directed intervention or an attention-matched control, delivered in weeks 13–20. The control matches contact time and contains no content on headache beliefs, coping or medication use. The primary outcome is monthly migraine days in weeks 21–24, analysed as the antibody-by-intervention interaction in a mixed model adjusted for baseline and week-12 frequency. The proposal predicts a larger effect of the interpretation-directed intervention in the antibody arm. With a standard deviation of 6 days, a two-sided α of 0.05 and baseline adjustment that removes 36% of the variance (correlation 0.6), about 155 participants per cell, 620 before attrition, give 90% power to detect an interaction of 2.5 migraine days per month, similar to the placebo-adjusted effect of erenumab in chronic migraine [18]. The proposal is supported if the lower 95% confidence limit of the interaction exceeds zero, and it counts against the proposal if the upper limit lies below 1.5 days; other results are inconclusive. At this size a true interaction of zero meets the second criterion about half the time, and about 430 participants per cell would give 90% power to refute. The test is void if the antibody arm does not have significantly fewer migraine days at week 12 than the placebo or delayed-start arm, and participants whose monthly migraine days rise by 30% or more over baseline receive rescue treatment, analysed as an intercurrent event. Adherence is recorded as a mediator. If better engagement once attacks are less frequent explains an effect, the clinical rule holds through a different mechanism. A two-sequence design, in which the antibody is started before or after the interpretation-directed intervention and continued once started, is a secondary option, with its endpoint at least eight weeks after the second component in both arms. Prediction 1 tests the rule most directly, and it fails if the two classes cannot be separated in patients.
Prediction 2. Process without frequency under high drive. In adults with chronic migraine who have at least 15 headache days per month on no preventive treatment, or on one unchanged for three months that has not reduced monthly migraine days by 30% or more, and without medication overuse, a standardised interpretation-directed intervention is compared with the control defined in Prediction 1. The proposal predicts improvement in self-efficacy, catastrophising and acceptance, and a between-group difference in monthly migraine days whose 95% confidence interval lies within ±1.5 days. A reduction whose 95% confidence interval lies entirely below −1.5 days counts against the proposal; other results are inconclusive. With a standard deviation of 5 to 6 days, 90% power and a true difference of zero, this needs about 290 to 420 participants per arm, or about 185 to 270 with baseline adjustment at a correlation of 0.6. A trial in which the control moves self-efficacy or catastrophising, or the intervention does not move them more than the control, is uninformative. Impact, measured with HIT-6 and MIDAS, is a secondary outcome for which the proposal predicts a smaller effect than in a parallel stratum with episodic migraine. That part was specified after the results in Section 4.2 and counts only if confirmed prospectively.
Prediction 3. Class membership predicts order dependence. In adults with chronic migraine and comorbid insomnia, behavioural treatment of insomnia and a mindfulness-based intervention are each given either before or after a CGRP-pathway antibody in a factorial design. The proposal predicts an order interaction for the mindfulness-based intervention and no order interaction for insomnia treatment. An order effect of similar size for both would assign the effect to timing in general and show the classification to be redundant, an order effect for insomnia treatment alone contradicts the classification, and the absence of an order effect for either counts against the rule. The test is a three-way interaction and needs a large multicentre sample, so Prediction 4 is the feasible first step. The ISPY trial tests an adjacent claim (Section 4.4).
Prediction 4. Moderation by achieved drive reduction. Within trials of an interpretation-directed intervention added to preventive treatment, the benefit on monthly migraine days should increase with the fall in migraine days achieved before the intervention began, entered as a continuous moderator and adjusted for baseline frequency and for the time since the drive-lowering treatment started. A moderation coefficient whose 95% confidence interval lies below 0.5 migraine days per month for each 25% pre-intervention reduction counts against the proposal, a lower limit above zero supports it, and other results are inconclusive. No completed trial identified in the search recorded diaries across a documented drive-lowering period before a purely interpretation-directed component was added. The closest are a trial of acceptance and commitment therapy added to prophylaxis that had been stable for three months [62] and MIND-CM, if diaries between withdrawal and the first mindfulness session exist [2]; the MIND-CM package is mixed, so it would test moderation of the package. Prediction 4 is therefore best built into new add-on trials, with diaries recorded from the start of the drive-lowering treatment. Because the pre-intervention fall is not randomised, responder phenotype, regression to the mean and floor effects have to be modelled.
Prediction 5. Order dependence of graded activity. In chronic migraine, graded activity and conditioning of the same modality, session length and planned dose differ in their progression rule, with graded activity following a preset time-contingent schedule and conditioning progressing as symptoms allow. Both are given either before or after a period of drive-lowering treatment, with make-up sessions scheduled and the dose actually delivered analysed. Aggravation by or avoidance of routine physical activity is a feature of migraine attacks [17], so the schedule is kept on days between attacks and on days with mild headache, and adverse events are monitored. The proposal predicts an order-by-condition interaction, with graded activity reducing migraine days more than conditioning when given after drive lowering, and both reducing kinesiophobia and increasing activity in either order. The proposal is supported if the lower 95% confidence limit of the interaction exceeds zero. It counts against the proposal if the upper limit of the order effect for graded activity lies below 1.5 migraine days per month, and against the classification if the 95% confidence interval for the difference between the order effects of the two arms lies within ±1.5 days; other results are inconclusive, and the test is void if migraine days fell by less than 30% during the drive-lowering period. Because the search identified no randomised trial of graded activity in migraine, a feasibility study of time-contingent progression during an active headache disorder has to come first.
Predictions for two current trials. For ISPY [15], the proposal predicts a larger reduction in headache days per 14-day diary during the pain-treatment phase, measured from the end of the first phase to the end of the second, in the arm that received insomnia treatment first. A lower 95% confidence limit for the between-arm difference in that change above zero supports the proposal. An upper limit below 0.5 day per 14 days, which rules out the predicted advantage and covers any significant result favouring the sleep-education arm, counts against it; other results are inconclusive, and at the size of ISPY a null result will often be inconclusive. The prediction is void if insomnia treatment did not reduce insomnia severity more than sleep education in the first phase. Because insomnia treatment may reduce headache days with a delay [40], a positive result cannot separate a better response to pain treatment from a delayed effect of insomnia treatment and counts as weak support. A registered trial will add four weeks of virtual-reality acceptance and mindfulness training to a stable CGRP-pathway antibody in episodic migraine with 4–10 migraine days per month, against continued antibody alone, with headache days at six months as its efficacy outcome. It was not yet recruiting on 23 September 2026 (ClinicalTrials.gov NCT07599228). The proposal predicts fewer headache days in the training arm. A 95% confidence interval whose lower limit lies above −1 headache day per month counts against it, and an upper limit below zero supports it weakly, because the comparator is not attention-matched; other results are inconclusive. The prediction is void if frequency before the antibody is not documented or fell by less than 30% on the antibody.
7. Discussion
7.1. Objections
Withdrawal is behavioural and comes first, which contradicts the thesis. It contradicts a version in which all non-pharmacological treatment follows the drug, and that version should be abandoned. Withdrawal of overused medication is proposed to lower drive and belongs in the first step, as does the guideline's first step, education and counselling to reduce the overused medication [37].
Education comes first in current recommendations. Grazzi and colleagues describe patient education as a first step of care [7], and in medication-overuse headache current recommendations favour a stepwise approach that begins with it [8]. In medication-overuse headache the education given first is largely advice to reduce the overused medication, which the rule in Section 3.1 places with withdrawal, and Table 1 separates it from education programmes aimed at beliefs and self-efficacy, which stay in the second class. Where education comes first for other reasons, such as orientation to the condition and its treatment, the proposal is compatible with it and predicts which outcomes it can move at that point.
Sequencing becomes gatekeeping. The clinical risk is real, since a rule that behavioural treatment comes second can be read as permission to withhold it, in a field where psychological treatment already faces barriers to implementation [7]. The rule in Section 5 places the behavioural drive-lowering treatments in the first step and offers interpretation-directed treatment alongside it when disability or distress is high, when the patient prefers it, when preventive treatment is unavailable, not tolerated or declined, and in pregnancy.
The classification could be adjusted after the fact. The rule in Section 3.1 takes each proposed mechanism from a cited source, codes packages by component and marks mixed cases, and Table 2 records the results that do not fit, from Holroyd 2010 [63] and a trial of acceptance and commitment therapy [62], together with the inconclusive result of Pijpers 2022 [39], whose point estimates run against the proposal, the reading of Powers 2013 [57] that counts against it, and the two results that contradict its stronger form. The reading rules were specified after the trials were known, so the tally in Section 4 is a structured description, and the predictions in Section 6 are the test. If further trials require repeated reassignment of interventions to preserve the pattern, the classification should be abandoned.
The field already recommends combining the two. Recent reviews describe psychological treatment as a means of enhancing the effect of medication [7]. A combination claim says that two treatments given together do better than either alone, which the Holroyd trial supports for frequency. The claim made here is stronger, since it says that one class works mainly in the presence of the other, and that the same two treatments can produce different outcomes depending on which comes first. Prediction 1 can refute it.
This is clinical common sense with a new label. In the author's experience, clinicians commonly treat medication overuse and insomnia before referring for psychological therapy and start prophylaxis in parallel. The proposal goes beyond that practice in two ways. It predicts which outcome each class should move, and it specifies trials whose results could show the rule to be wrong. The studies that compared the two classes in both orders were small (Section 4.4).
The CHESS and MIND-CM contrast is confounded. The trials differ in intensity, therapist contact, country, health-care setting and the prevalence of medication overuse, and the MIND-CM protocol also targeted medication use. The comparison identifies one difference among several and cannot establish that it is the operative one. The reading in Section 4 motivates the tests in Section 6.
The trials show regression to the mean and placebo response. Migraine days fell by 1.6 and 2.0 in the two arms of the Wells trial, and headache days fell by 6.8 in the education arm of the Powers trial. Within-arm changes are therefore uninformative, and the predictions rely on between-group and order-based comparisons.
7.2. Implications for Trial Design
If the two classes are mixed within a single category, trials of that category will continue to produce heterogeneous results, and systematic reviews will continue to find them difficult to pool. Trials of interpretation-directed interventions should report, and ideally control, the drive-lowering treatment in place at randomisation, which in several trials reviewed here is described only as usual care. Packages should be reported by component, in line with the call of the 2025 systematic review to standardise intervention components [6]. Primary outcomes can be chosen to match the class, with attack frequency for drive-lowering interventions and self-efficacy, impact, disability and acceptance for interpretation-directed ones, and the other reported as secondary. Trials of combinations can be designed to estimate a conditional or order effect as well as an additive one. RESOLUTION, in which brief education was held constant while the antibody was randomised, shows that components can be separated in a large multinational trial [35].
Monteith and colleagues describe current options as tending to be binary, either medication or behavioural intervention, and call for studies of combinations and of sequencing that include CGRP-targeted treatment [9]. The registered virtual-reality trial in Section 6 adds the second step with the first in place and does not vary order. A registered feasibility trial with sequential multiple assignment will randomise, or let participants choose, pairs of lifestyle components of a virtually delivered behavioural programme, namely regular meals, regular sleep and timed exercise, and will study their combinations and sequences (ClinicalTrials.gov NCT06170281); regular meals and sleep act on drive under the classification, and the proposal predicts little dependence on their order.
7.3. Limitations
The argument concerns chronic migraine, where a molecular handle on the ascending pathway exists and the outcome can be counted in days. Several of the trials read here were in episodic migraine (among them Wells, Holroyd, Varkey, Seminowicz, Klan and Grazzi 2021), in adolescents (Powers, ISPY) or in mixed chronic headache (CHESS, Thorn), and conclusions drawn from them carry over to adult chronic migraine only in part. Outcome measures differ between trials, among them migraine days, headache days, migraines per 30 days and responder rates, which limits comparison. The classification of multicomponent packages depends on how completely trial reports describe their content. The two-class model simplifies a system in which drive and interpretation interact continuously. The proposal requires that interventions can be ranked by which side they act on, and that this ranking predicts an effect of order or of drive status that can be measured. Whether the proposed mechanism explains such an effect, should it be found, is a further question. This is a narrative review, and although the search was logged, study selection and the readings in Table 2 were made by one author, with reading rules specified after the trials were known.
8. Conclusions
When the randomised trials reviewed here are grouped by mechanism, treatments that lower nociceptive drive reduce attack frequency, and treatments directed at interpretation improved process measures such as self-efficacy in most trials that measured them. Disability improved more in episodic than in chronic migraine in one planned analysis, and no trial identified isolated whether these treatments reduce frequency after a documented fall in drive. Most psychological packages tested so far combine components of both classes, and some trials do not fit the pattern. The rule that follows concerns drive-lowering and interpretation-directed treatment rather than drugs and behaviour. It is to start drive-lowering treatment first, including its behavioural forms, and to offer interpretation-directed treatment alongside it when waiting would be inappropriate. A factorial trial of the conditional effect and a moderation analysis built into add-on trials would test the rule, and the stated predictions for two current trials would test parts of it.
Author Contributions
G.A.S. conceived the argument and the classification, directed the literature search, reviewed and revised all drafts, and approved the final manuscript. The use of artificial intelligence is described in Section 2.2.
Funding
No funding was received for this work.
Data Availability Statement
No datasets were generated or analysed. The search strategy is described in Section 2.1, and the query log with record counts is provided as Supplementary File 1.
Conflicts of Interest
The author declares no competing interests.
Human and Animal Rights and Informed Consent
This article does not contain any studies with human or animal subjects performed by the author.
References
- Underwood, M.; Achana, F.; Carnes, D.; Eldridge, S.; Ellard, D.R.; Griffiths, F.; et al. Supportive self-management program for people with chronic headaches and migraine: a randomized controlled trial and economic evaluation. Neurology 2023, 100(13), e1339–e1352. [Google Scholar] [CrossRef] [PubMed]
- Grazzi, L.; D'Amico, D.; Guastafierro, E.; Demichelis, G.; Erbetta, A.; Fedeli, D.; et al. Efficacy of mindfulness added to treatment as usual in patients with chronic migraine and medication overuse headache: a phase-III single-blind randomized-controlled trial (the MIND-CM study). J. Headache Pain 2023, 24(1), 86. [Google Scholar] [CrossRef] [PubMed]
- Hailston, A.; Davies, N.; Ratna, M.; Matharu, M.; Underwood, M. The effectiveness of educational, behavioural, and cognitive self-management support interventions for chronic migraine: a systematic review. Prim. Health Care Res. Dev. 2025, 26, e98. [Google Scholar] [CrossRef] [PubMed]
- Onan, D.; Christensen, R.H.; Kodounis, M.; Krøll, L.S.; Szabo, E.; Ornello, R.; et al. Non-pharmacological treatments of migraine: current evidence and clinical practice. Curr. Pain Headache Rep. 2026, 30(1), 91. [Google Scholar] [CrossRef] [PubMed]
- Han, X.; Yu, S. Non-pharmacological treatment for chronic migraine. Curr. Pain Headache Rep. 2023, 27(11), 663–672. [Google Scholar] [CrossRef] [PubMed]
- Treadwell, J.R.; Tsou, A.Y.; Rouse, B.; Ivlev, I.; Fricke, J.; Buse, D.C.; et al. Behavioral interventions for migraine prevention: a systematic review and meta-analysis. Headache 2025, 65(4), 668–694. [Google Scholar] [CrossRef] [PubMed]
- Grazzi, L.; Rizzoli, P.B.; Montisano, D.A.; Lambru, G.; Raggi, A. Psychological interventions for migraine. Nat. Rev. Neurol. 2026, 22(7), 411–427. [Google Scholar] [CrossRef] [PubMed]
- Messina, R.; Castaldo, M.; Ha, W.S.; Labastida-Ramirez, A.; Yener, S.M.; Onofri, A.; et al. Breaking the medication overuse headache cycle: from nociplastic pain mechanisms to patient-centered interventions – the Junior Editorial Board vision. J. Headache Pain 2026, 27(1), 108. [Google Scholar] [CrossRef] [PubMed]
- Monteith, T.S.; Lazaridou, A.; Bernstein, C. Combination behavioral and pharmacological interventions through telehealth platforms: opportunities for increasing access and optimizing migraine outcomes. Headache 2025, 65(8), 1276–1278. [Google Scholar] [CrossRef] [PubMed]
- Blanchard, E.B.; Appelbaum, K.A.; Radnitz, C.L.; Jaccard, J.; Dentinger, M.P. The refractory headache patient–I. Chronic, daily, high intensity headache. Behav. Res. Ther. 1989, 27(4), 403–410. [Google Scholar] [CrossRef] [PubMed]
- Michultka, D.M.; Blanchard, E.B.; Appelbaum, K.A.; Jaccard, J.; Dentinger, M.P. The refractory headache patient–II. High medication consumption (analgesic rebound) headache. Behav. Res. Ther. 1989, 27(4), 411–420. [Google Scholar] [CrossRef] [PubMed]
- Calhoun, A.H.; Ford, S. Behavioral sleep modification may revert transformed migraine to episodic migraine. Headache 2007, 47(8), 1178–1183. [Google Scholar] [CrossRef] [PubMed]
- Walker, D.; Zhang, N.; Natbony, L.R. Insomnia and migraine: a review of evidence-based, biobehavioral interventions. Curr. Pain Headache Rep. 2023, 27(2), 19–25. [Google Scholar] [CrossRef] [PubMed]
- Palermo, T.M.; Law, E.F.; Kim, A.; de la Vega, R.; Zhou, C. Baseline sleep disturbances modify outcome trajectories in adolescents with chronic pain receiving internet-delivered psychological treatment. J. Pain 2022, 23(7), 1245–1255. [Google Scholar] [CrossRef] [PubMed]
- Law, E.F.; Ritterband, L.; Zhou, C.; Palermo, T.M. Intervention for Sleep and Pain in Youth (ISPY-RCT): protocol for a two-phase randomized controlled trial of sequenced cognitive-behavioral therapy for insomnia and pain management in adolescents with migraine. Trials 2023, 24(1), 25. [Google Scholar] [CrossRef] [PubMed]
- Woldeamanuel, Y.W. Editorial: rethink your exercise for precision migraine management. Headache 2026, 66(1), 11–14. [Google Scholar] [CrossRef] [PubMed]
- Headache Classification Committee of the International Headache Society (IHS). The International Classification of Headache Disorders, 3rd edition. Cephalalgia 2018, 38(1), 1–211. [Google Scholar] [CrossRef] [PubMed]
- Tepper, S.; Ashina, M.; Reuter, U.; Brandes, J.L.; Doležil, D.; Silberstein, S.; et al. Safety and efficacy of erenumab for preventive treatment of chronic migraine: a randomised, double-blind, placebo-controlled phase 2 trial. Lancet Neurol. 2017, 16(6), 425–434. [Google Scholar] [CrossRef] [PubMed]
- Silberstein, S.D.; Dodick, D.W.; Bigal, M.E.; Yeung, P.P.; Goadsby, P.J.; Blankenbiller, T.; et al. Fremanezumab for the preventive treatment of chronic migraine. N Engl. J. Med. 2017, 377(22), 2113–2122. [Google Scholar] [CrossRef] [PubMed]
- Detke, H.C.; Goadsby, P.J.; Wang, S.; Friedman, D.I.; Selzler, K.J.; Aurora, S.K. Galcanezumab in chronic migraine: the randomized, double-blind, placebo-controlled REGAIN study. Neurology 2018, 91(24), e2211–e2221. [Google Scholar] [CrossRef] [PubMed]
- Lipton, R.B.; Goadsby, P.J.; Smith, J.; Schaeffler, B.A.; Biondi, D.M.; Hirman, J.; et al. Efficacy and safety of eptinezumab in patients with chronic migraine: PROMISE-2. Neurology 2020, 94(13), e1365–e1377. [Google Scholar] [CrossRef] [PubMed]
- Sacco, S.; Amin, F.M.; Ashina, M.; Bendtsen, L.; Deligianni, C.I.; Gil-Gouveia, R.; et al. European Headache Federation guideline on the use of monoclonal antibodies targeting the calcitonin gene related peptide pathway for migraine prevention – 2022 update. J. Headache Pain 2022, 23(1), 67. [Google Scholar] [CrossRef] [PubMed]
- Puledda, F.; Sacco, S.; Diener, H.C.; Ashina, M.; Al-Khazali, H.M.; Ashina, S.; et al. International Headache Society global practice recommendations for preventive pharmacological treatment of migraine. Cephalalgia 2024, 44(9), 3331024241269735. [Google Scholar] [CrossRef] [PubMed]
- Edvinsson, L.; Haanes, K.A.; Warfvinge, K.; Krause, D.N. CGRP as the target of new migraine therapies – successful translation from bench to clinic. Nat. Rev. Neurol. 2018, 14(6), 338–350. [Google Scholar] [CrossRef] [PubMed]
- Migraine, Ashina M. N Engl. J. Med. 2020, 383(19), 1866–1876. [CrossRef] [PubMed]
- Burstein, R.; Noseda, R.; Borsook, D. Migraine: multiple processes, complex pathophysiology. J. Neurosci. 2015, 35(17), 6619–6629. [Google Scholar] [CrossRef] [PubMed]
- Louter, M.A.; Bosker, J.E.; van Oosterhout, W.P.; van Zwet, E.W.; Zitman, F.G.; Ferrari, M.D.; et al. Cutaneous allodynia as a predictor of migraine chronification. Brain 2013, 136 Pt 11, 3489–3496. [Google Scholar] [CrossRef] [PubMed]
- Rogers, A.H.; Farris, S.G. A meta-analysis of the associations of elements of the fear-avoidance model of chronic pain with negative affect, depression, anxiety, pain-related disability and pain intensity. Eur. J. Pain 2022, 26(8), 1611–1635. [Google Scholar] [CrossRef] [PubMed]
- Vlaeyen, J.W.S.; Crombez, G.; Linton, S.J. The fear-avoidance model of pain. Pain 2016, 157(8), 1588–1589. [Google Scholar] [CrossRef] [PubMed]
- Tolentino, G.A.; Florencio, L.L.; Pinheiro-Araújo, C.F.; Martins, J.; Chaves, T.C.; Norato, A.C.C.; et al. Evaluation of maladaptive beliefs in patients with migraine: measurement properties for three versions (TSK-11, TSK-13, and TSK-17) of the Tampa Scale for Kinesiophobia. Braz. J. Phys. Ther. 2024, 28(4), 101093. [Google Scholar] [CrossRef] [PubMed]
- Penzien, D.B.; Irby, M.B. Biobehavioral treatments of migraine. Handb. Clin. Neurol. 2024, 199, 155–169. [Google Scholar] [CrossRef] [PubMed]
- Eckert, A.L.; Pabst, K.; Endres, D.M. A Bayesian model for chronic pain. Front Pain Res. 2022, 3, 966034. [Google Scholar] [CrossRef] [PubMed]
- Eippert, F.; Finsterbusch, J.; Bingel, U.; Büchel, C. Direct evidence for spinal cord involvement in placebo analgesia. Science 2009, 326(5951), 404. [Google Scholar] [CrossRef] [PubMed]
- Krøll, L.S.; Sjödahl Hammarlund, C.; Gard, G.; Jensen, R.H.; Bendtsen, L. Has aerobic exercise effect on pain perception in persons with migraine and coexisting tension-type headache and neck pain? A randomized, controlled, clinical trial. Eur. J. Pain 2018, 22(8), 1399–1408. [Google Scholar] [CrossRef] [PubMed]
- Jensen, R.H.; Lundqvist, C.; Schytz, H.W.; Tassorelli, C.; Vernieri, F.; Lanteri-Minet, M.; et al. Eptinezumab with patient education for chronic migraine and medication-overuse headache: the randomized, placebo-controlled RESOLUTION trial. Neurology 2026, 106(8), e214863. [Google Scholar] [CrossRef] [PubMed]
- Schytz, H.W.; Jensen, R.H.; Lundqvist, C.; Tassorelli, C.; Vernieri, F.; Lantéri-Minet, M.; et al. Efficacy and safety of eptinezumab in adults with chronic migraine and medication-overuse headache who also received patient education: 24-week results of the randomized RESOLUTION trial. J. Headache Pain 2026, 27(1), 157. [Google Scholar] [CrossRef] [PubMed]
- Diener, H.C.; Antonaci, F.; Braschinsky, M.; Evers, S.; Jensen, R.; Lainez, M.; et al. European Academy of Neurology guideline on the management of medication-overuse headache. Eur. J. Neurol. 2020, 27(7), 1102–1116. [Google Scholar] [CrossRef] [PubMed]
- Carlsen, L.N.; Munksgaard, S.B.; Nielsen, M.; Engelstoft, I.M.S.; Westergaard, M.L.; Bendtsen, L.; et al. Comparison of 3 treatment strategies for medication overuse headache: a randomized clinical trial. JAMA Neurol. 2020, 77(9), 1069–1078. [Google Scholar] [CrossRef] [PubMed]
- Pijpers, J.A.; Kies, D.A.; van Zwet, E.W.; Rosendaal, F.R.; Terwindt, G.M. Behavioural intervention in medication overuse headache: a concealed double-blind randomized controlled trial. Eur. J. Neurol. 2022, 29(5), 1496–1504. [Google Scholar] [CrossRef] [PubMed]
- Smitherman, T.A.; Walters, A.B.; Davis, R.E.; Ambrose, C.E.; Roland, M.; Houle, T.T.; et al. Randomized controlled pilot trial of behavioral insomnia treatment for chronic migraine with comorbid insomnia. Headache 2016, 56(2), 276–291. [Google Scholar] [CrossRef] [PubMed]
- Smitherman, T.A.; Kuka, A.J.; Calhoun, A.H.; Walters, A.B.P.; Davis-Martin, R.E.; Ambrose, C.E.; et al. Cognitive-behavioral therapy for insomnia to reduce chronic migraine: a sequential Bayesian analysis. Headache 2018, 58(7), 1052–1059. [Google Scholar] [CrossRef] [PubMed]
- Sforza, M.; Mariani, I.; Fazzini, F.; Genovese, F.; Salibba, A.; Filippi, M.; et al. Interventions for migraine and sleep: a systematic review exploring their bidirectional association. Eur. J. Neurol. 2026, 33(3), e70420. [Google Scholar] [CrossRef] [PubMed]
- Golovacheva, V.A.; Golovacheva, A.A.; Fateeva, T.G.; Parfenov, V.A. Cognitive behavioral therapy in the treatment of patients with chronic migraine and concomitant chronic insomnia: a prospective, randomized trial. Zh Nevrol. Psikhiatr Im. S S Korsakova (in Russian). 2024, 124(5 Vyp 2), 110–117. [Google Scholar] [CrossRef] [PubMed]
- Spierings, E.L.; McAllister, P.J.; Bilchik, T.R. Efficacy of treatment of insomnia in migraineurs with eszopiclone (Lunesta®) and its effect on total sleep time, headache frequency, and daytime functioning: a randomized, double-blind, placebo-controlled, parallel-group, pilot study. Cranio 2015, 33(2), 115–121. [Google Scholar] [CrossRef] [PubMed]
- Ramsden, C.E.; Zamora, D.; Faurot, K.R.; MacIntosh, B.; Horowitz, M.; Keyes, G.S.; et al. Dietary alteration of n-3 and n-6 fatty acids for headache reduction in adults with migraine: randomized controlled trial. BMJ 2021, 374, n1448. [Google Scholar] [CrossRef] [PubMed]
- Smelt, A.F.; Assendelft, W.J.; Terwee, C.B.; Ferrari, M.D.; Blom, J.W. What is a clinically relevant change on the HIT-6 questionnaire? An estimation in a primary-care population of migraine patients. Cephalalgia 2014, 34(1), 29–36. [Google Scholar] [CrossRef] [PubMed]
- Underwood, M.; Achana, F.; Carnes, D.; Eldridge, S.; Ellard, D.R.; Griffiths, F.; et al. Non-pharmacological educational and self-management interventions for people with chronic headache: the CHESS research programme including a RCT. Programme Grants Appl. Res. 2023, 11(2), 1–107. [Google Scholar] [CrossRef] [PubMed]
- Thorn, B.E.; Pence, L.B.; Ward, L.C.; Kilgo, G.; Clements, K.L.; Cross, T.H.; et al. A randomized clinical trial of targeted cognitive behavioral treatment to reduce catastrophizing in chronic headache sufferers. J. Pain 2007, 8(12), 938–949. [Google Scholar] [CrossRef] [PubMed]
- Fox, J.; Gaul, C.; Peperkorn, N.L.; Ohse, J.; Krutzki, J.; Körber, J.; et al. Targeting individual pain catastrophizing to reduce migraine-related disability: a randomized controlled proof-of-concept trial using an online CBT intervention. Sci. Rep. 2026, 16(1), 27238. [Google Scholar] [CrossRef] [PubMed]
- Seng, E.K.; Singer, A.B.; Metts, C.; Grinberg, A.S.; Patel, Z.S.; Marzouk, M.; et al. Does mindfulness-based cognitive therapy for migraine reduce migraine-related disability in people with episodic and chronic migraine? A phase 2b pilot randomized clinical trial. Headache 2019, 59(9), 1448–1467. [Google Scholar] [CrossRef] [PubMed]
- Seng, E.K.; Conway, A.B.; Grinberg, A.S.; Patel, Z.S.; Marzouk, M.; Rosenberg, L.; et al. Response to mindfulness-based cognitive therapy differs between chronic and episodic migraine. Neurol. Clin. Pract. 2021, 11(3), 194–205. [Google Scholar] [CrossRef] [PubMed]
- Klan, T.; Gaul, C.; Liesering-Latta, E.; Both, B.; Held, I.; Hennemann, S.; et al. Efficacy of cognitive-behavioral therapy for the prophylaxis of migraine in adults: a three-armed randomized controlled trial. Front Neurol. 2022, 13, 852616. [Google Scholar] [CrossRef] [PubMed]
- Seminowicz, D.A.; Burrowes, S.A.B.; Kearson, A.; Zhang, J.; Krimmel, S.R.; Samawi, L.; et al. Enhanced mindfulness-based stress reduction in episodic migraine: a randomized clinical trial with magnetic resonance imaging outcomes. Pain 2020, 161(8), 1837–1846. [Google Scholar] [CrossRef] [PubMed]
- Simshäuser, K.; Pohl, R.; Behrens, P.; Schultz, C.; Lahmann, C.; Schmidt, S. Mindfulness-based cognitive therapy as migraine intervention: a randomized waitlist controlled trial. Int. J. Behav. Med. 2022, 29(5), 597–609. [Google Scholar] [CrossRef] [PubMed]
- Simshäuser, K.; Lüking, M.; Kaube, H.; Schultz, C.; Schmidt, S. Is mindfulness-based stress reduction a promising and feasible intervention for patients suffering from migraine? A randomized controlled pilot trial. Complement Med. Res. 2020, 27(1), 19–30. [Google Scholar] [CrossRef] [PubMed]
- Wells, R.E.; O'Connell, N.; Pierce, C.R.; Estave, P.; Penzien, D.B.; Loder, E.; et al. Effectiveness of mindfulness meditation vs headache education for adults with migraine: a randomized clinical trial. JAMA Intern Med. 2021, 181(3), 317–328. [Google Scholar] [CrossRef] [PubMed]
- Powers, S.W.; Kashikar-Zuck, S.M.; Allen, J.R.; LeCates, S.L.; Slater, S.K.; Zafar, M.; et al. Cognitive behavioral therapy plus amitriptyline for chronic migraine in children and adolescents: a randomized clinical trial. JAMA 2013, 310(24), 2622–2630. [Google Scholar] [CrossRef] [PubMed]
- Powers, S.W.; Coffey, C.S.; Chamberlin, L.A.; Ecklund, D.J.; Klingner, E.A.; Yankey, J.W.; et al. Trial of amitriptyline, topiramate, and placebo for pediatric migraine. N Engl. J. Med. 2017, 376(2), 115–124. [Google Scholar] [CrossRef] [PubMed]
- Polk, A.N.; Smitherman, T.A. A meta-analytic review of acceptance-based interventions for migraine. Headache 2023, 63(9), 1271–1284. [Google Scholar] [CrossRef] [PubMed]
- Liao, Y.C.; Chen, W.S.; Restya, W.P.D.; Liao, Y.C.; Lin, Y.C.; Lin, R.T. Effectiveness and influence of mindfulness-based intervention on migraine patients: a systematic review and meta-analysis. J. Psychosom. Res. 2025, 197, 112366. [Google Scholar] [CrossRef] [PubMed]
- Grazzi, L.; Sansone, E.; Raggi, A.; D'Amico, D.; De Giorgio, A.; Leonardi, M.; et al. Mindfulness and pharmacological prophylaxis after withdrawal from medication overuse in patients with chronic migraine: an effectiveness trial with a one-year follow-up. J. Headache Pain 2017, 18(1), 15. [Google Scholar] [CrossRef] [PubMed]
- Grazzi, L.; Andrasik, F.; Rizzoli, P.; Bernstein, C.; Sansone, E.; Raggi, A. Acceptance and commitment therapy for high frequency episodic migraine without aura: findings from a randomized pilot investigation. Headache 2021, 61(6), 895–905. [Google Scholar] [CrossRef] [PubMed]
- Holroyd, K.A.; Cottrell, C.K.; O'Donnell, F.J.; Cordingley, G.E.; Drew, J.B.; Carlson, B.W.; et al. Effect of preventive (beta blocker) treatment, behavioural migraine management, or their combination on outcomes of optimised acute treatment in frequent migraine: randomised controlled trial. BMJ 2010, 341, c4871. [Google Scholar] [CrossRef] [PubMed]
- Seng, E.K.; Holroyd, K.A. Behavioral migraine management modifies behavioral and cognitive coping in people with migraine. Headache 2014, 54(9), 1470–1483. [Google Scholar] [CrossRef] [PubMed]
- Knapp, T.W. Treating migraine by training in temporal artery vasoconstriction and/or cognitive behavioral coping: a one-year follow-up. J. Psychosom. Res. 1982, 26(5), 551–557. [Google Scholar] [CrossRef] [PubMed]
- Kropp, P.; Gerber, W.D.; Keinath-Specht, A.; Kopal, T.; Niederberger, U. Behavioral treatment in migraine. Cognitive-behavioral therapy and blood-volume-pulse biofeedback: a cross-over study with a two-year follow-up. Funct. Neurol. 1997, 12(1), 17–24. [Google Scholar] [PubMed]
- Woldeamanuel, Y.W.; Oliveira, A.B.D. What is the efficacy of aerobic exercise versus strength training in the treatment of migraine? A systematic review and network meta-analysis of clinical trials. J. Headache Pain 2022, 23(1), 134. [Google Scholar] [CrossRef] [PubMed]
- Reina-Varona, Á.; Madroñero-Miguel, B.; Fierro-Marrero, J.; Paris-Alemany, A.; La Touche, R. Efficacy of various exercise interventions for migraine treatment: a systematic review and network meta-analysis. Headache 2024, 64(7), 873–900. [Google Scholar] [CrossRef] [PubMed]
- Varkey, E.; Cider, A.; Carlsson, J.; Linde, M. Exercise as migraine prophylaxis: a randomized study using relaxation and topiramate as controls. Cephalalgia 2011, 31(14), 1428–1438. [Google Scholar] [CrossRef] [PubMed]
- Krøll, L.S.; Hammarlund, C.S.; Linde, M.; Gard, G.; Jensen, R.H. The effects of aerobic exercise for persons with migraine and co-existing tension-type headache and neck pain. A randomized, controlled, clinical trial. Cephalalgia 2018, 38(12), 1805–1816. [Google Scholar] [CrossRef] [PubMed]
- Rice, D.; Nijs, J.; Kosek, E.; Wideman, T.; Hasenbring, M.I.; Koltyn, K.; et al. Exercise-induced hypoalgesia in pain-free and chronic pain populations: state of the art and future directions. J. Pain 2019, 20(11), 1249–1266. [Google Scholar] [CrossRef] [PubMed]
- Gatzounis, R.; Schrooten, M.G.; Crombez, G.; Vlaeyen, J.W. Operant learning theory in pain and chronic pain rehabilitation. Curr. Pain Headache Rep. 2012, 16(2), 117–126. [Google Scholar] [CrossRef] [PubMed]
- Magalhaes, M.O.; França, F.J.; Burke, T.N.; Ramos, L.A.; de Moura Campos Carvalho e Silva, A.P.; Almeida, G.P.; et al. Efficacy of graded activity versus supervised exercises in patients with chronic non-specific low back pain: protocol of a randomised controlled trial. BMC Musculoskelet. Disord. 2013, 14, 36. [Google Scholar] [CrossRef] [PubMed]
- Macedo, L.G.; Smeets, R.J.; Maher, C.G.; Latimer, J.; McAuley, J.H. Graded activity and graded exposure for persistent nonspecific low back pain: a systematic review. Phys. Ther. 2010, 90(6), 860–879. [Google Scholar] [CrossRef] [PubMed]
- Reina-Varona, Á.; Madroñero-Miguel, B.; Paris-Alemany, A.; La Touche, R. Perceived fear and exercise difficulty in patients with migraine and their association with psychosocial factors: a cross-sectional study. PeerJ. 2025, 13, e19342. [Google Scholar] [CrossRef] [PubMed]
- La Touche, R.; de Oliveira, A.B.; Paris-Alemany, A.; Reina-Varona, Á. Incorporating therapeutic education and exercise in migraine management: a biobehavioral approach. J. Clin. Med. 2024, 13(20), 6273. [Google Scholar] [CrossRef] [PubMed]
- den Hollander, M.; Goossens, M.; de Jong, J.; Ruijgrok, J.; Oosterhof, J.; Onghena, P.; et al. Expose or protect? A randomized controlled trial of exposure in vivo vs pain-contingent treatment as usual in patients with complex regional pain syndrome type 1. Pain 2016, 157(10), 2318–2329. [Google Scholar] [CrossRef] [PubMed]
- Kyle, S.D.; Miller, C.B.; Rogers, Z.; Siriwardena, A.N.; Macmahon, K.M.; Espie, C.A. Sleep restriction therapy for insomnia is associated with reduced objective total sleep time, increased daytime somnolence, and objectively impaired vigilance: implications for the clinical management of insomnia disorder. Sleep 2014, 37(2), 229–237. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Two axes of intervention in chronic migraine and the proposed consequence of order. The horizontal axis is ascending nociceptive drive, lowered by CGRP-pathway treatment, withdrawal of overused acute medication, behavioural treatment of insomnia and dietary alteration of fatty acids. The vertical axis is the weight given to the pain interpretation, lowered by the cognitive components of cognitive-behavioural therapy, mindfulness, acceptance and commitment therapy, belief-oriented education and graded activity. Trials are placed by the step they randomised: a drive-lowering step (Ramsden 2021, RESOLUTION 2026), a mixed mindfulness package added to withdrawal and prophylaxis (MIND-CM 2023), and interpretation-directed treatment without a documented drive-lowering step (CHESS 2023, Thorn 2007). The proposal is that movement along the vertical axis reduces attack frequency mainly after movement along the horizontal axis, so that the two routes to the lower left corner are not equivalent.
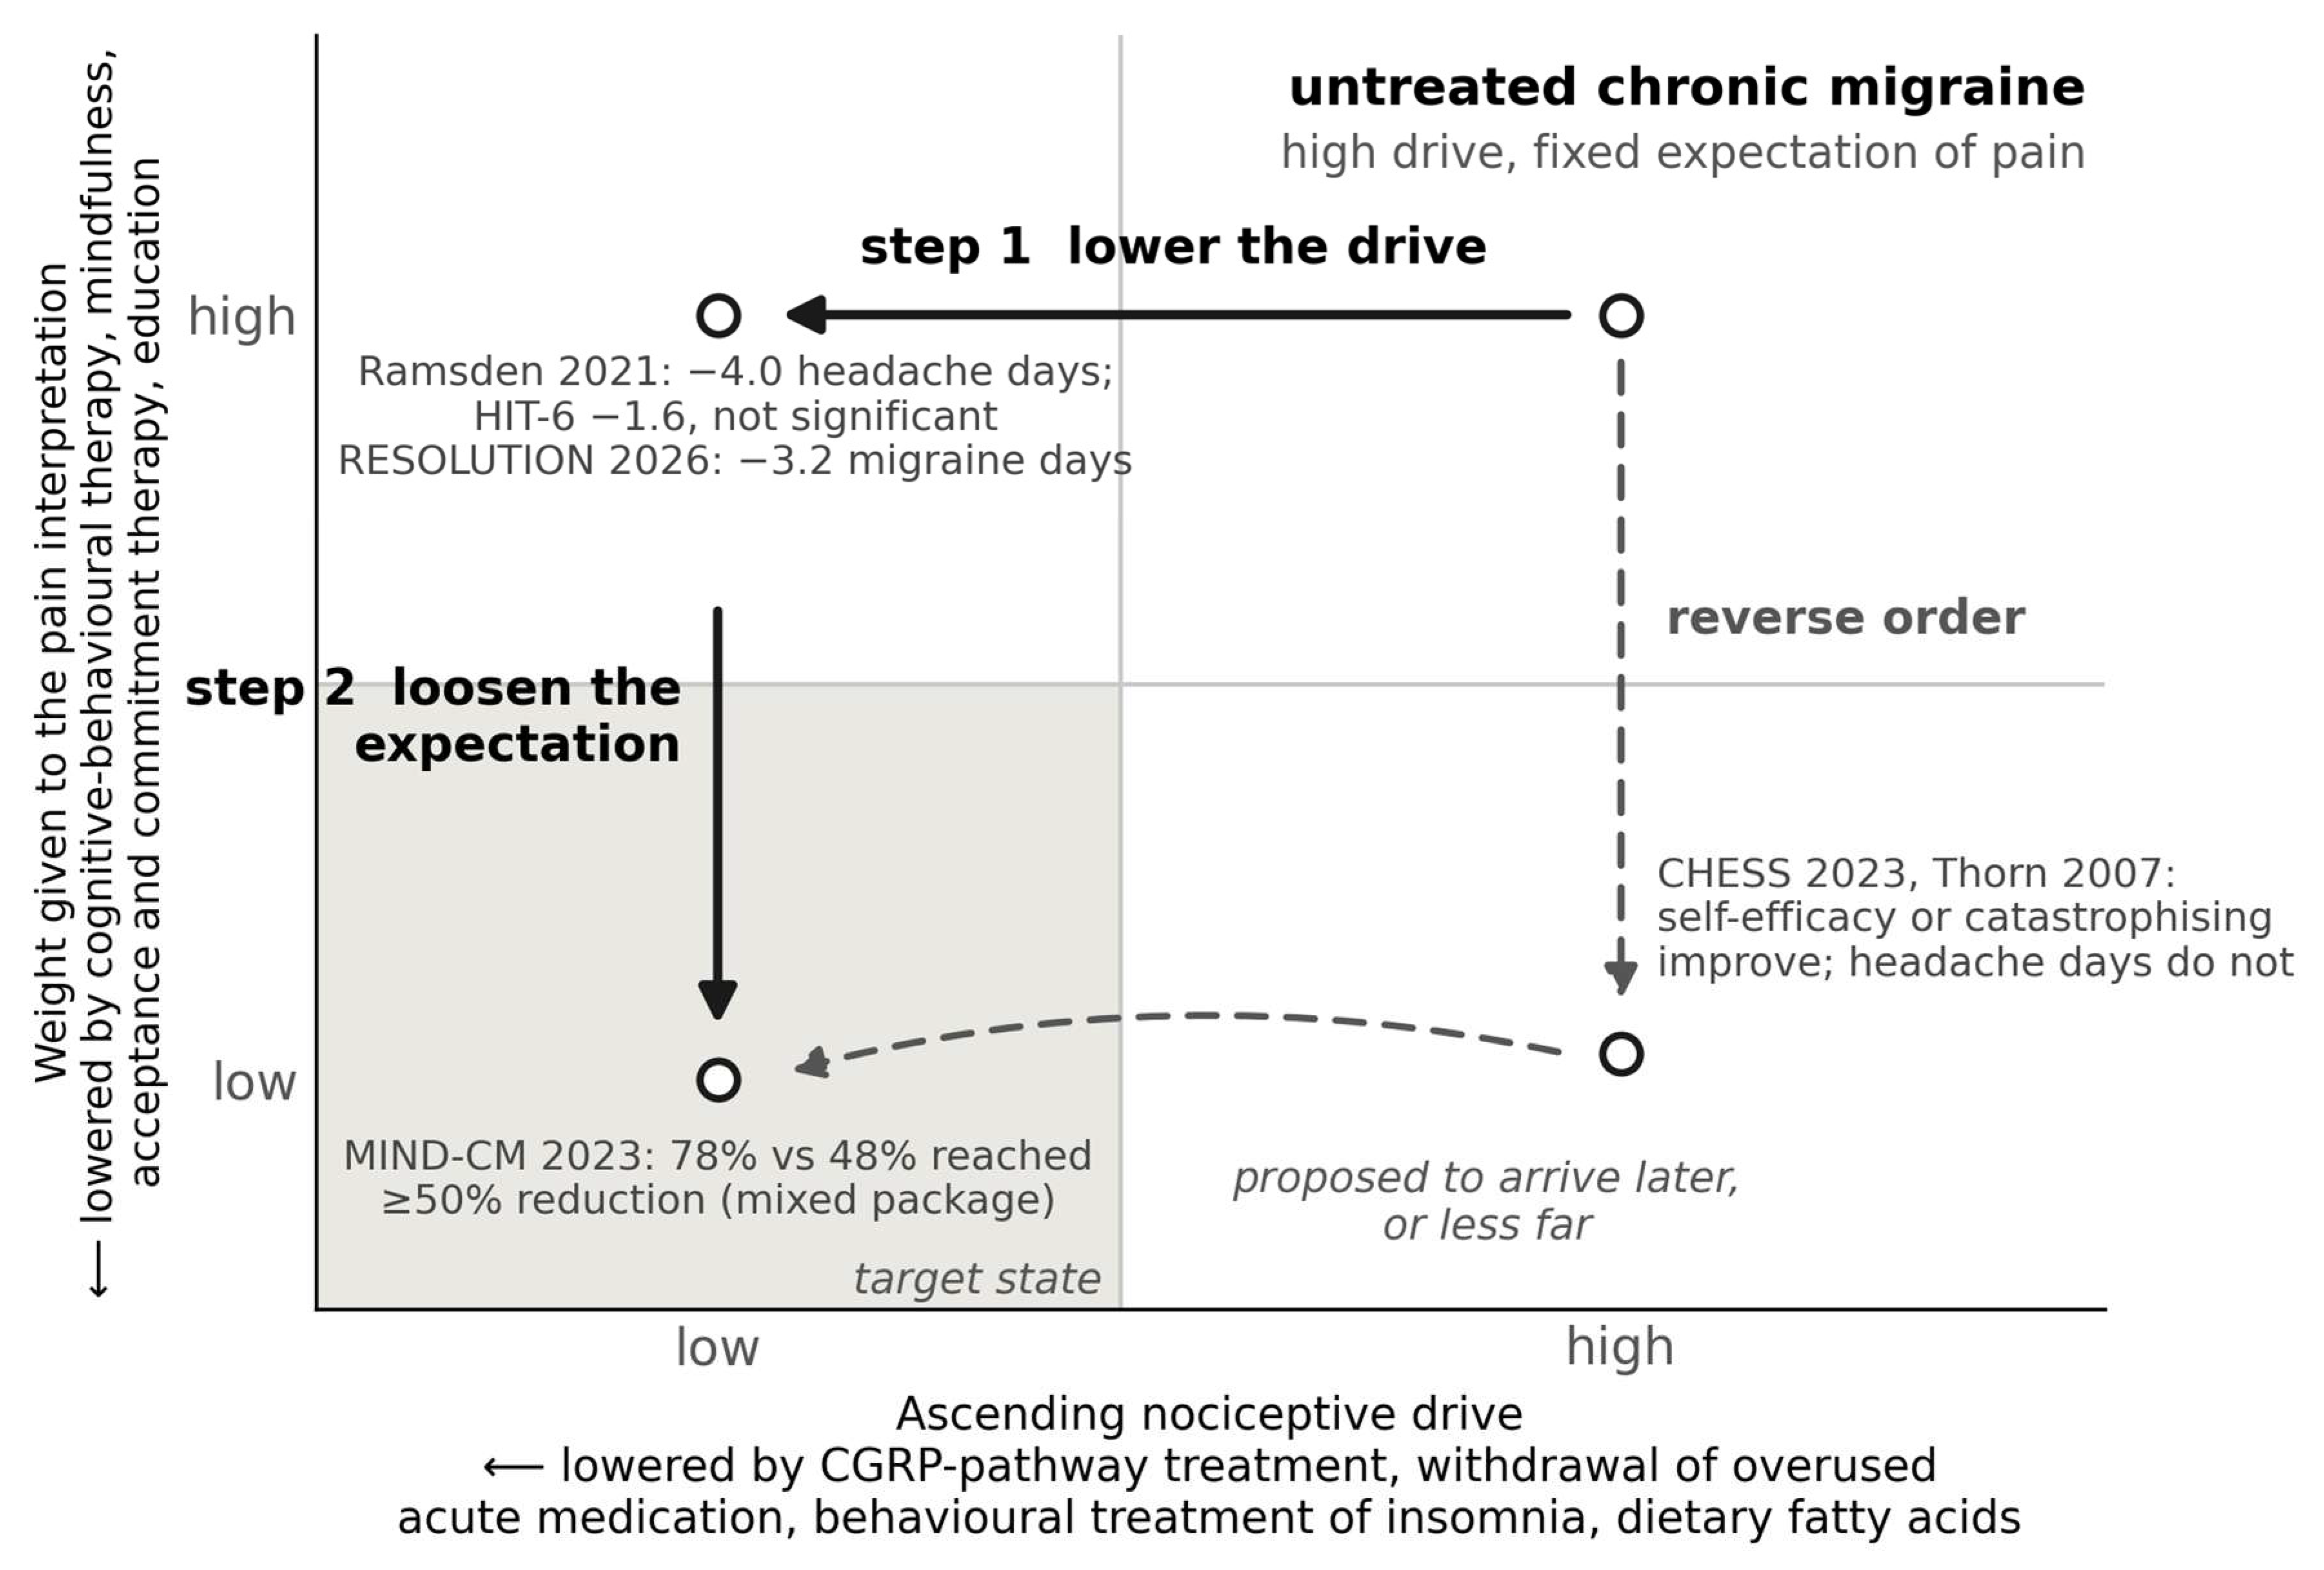
Table 1.
Classification of non-pharmacological treatments in migraine by proposed mechanism. The mechanism is taken from the cited trial reports and reviews; treatments with components acting on both sides are classed as mixed.
Table 1.
Classification of non-pharmacological treatments in migraine by proposed mechanism. The mechanism is taken from the cited trial reports and reviews; treatments with components acting on both sides are classed as mixed.
| Intervention | Proposed mechanism (source) | Class | Mediator for the manipulation check | Order prediction |
|---|---|---|---|---|
| Withdrawal of overused acute medication, including education, counselling and support whose aim is withdrawal | removal of a pharmacologically maintained generator of headache [8,37] | drive-lowering | acute-medication days | first step; no order effect |
| Behavioural treatment of comorbid insomnia (stimulus control, sleep restriction) | removal of sleep disturbance as a trigger of attacks [40]; hypothesised benefit of sleep modification [12] | drive-lowering | insomnia severity, sleep time | first step; no order effect |
| Dietary alteration of n-3 and n-6 fatty acids | shift in nociceptive and antinociceptive lipid mediators [45] | drive-lowering | 17-hydroxydocosahexaenoic acid | first step; no order effect |
| Aerobic or strength conditioning | exercise-induced hypoalgesia [71]; reduced avoidance, proposed after a null mechanistic result [34] | mixed; uninformative | – | not predicted |
| Graded activity with time-contingent progression | reduction of avoidance behaviour by operant methods [29,72] | interpretation-directed | activity level, kinesiophobia | second step; order effect predicted |
| Cognitive components of cognitive-behavioural therapy (cognitive restructuring, coping skills) | change in appraisal, catastrophising and coping [48,64] | interpretation-directed; packages adding relaxation or biofeedback are mixed | catastrophising, self-efficacy | second step; order effect predicted |
| Mindfulness-based interventions, meditation components | change in attention to and acceptance of bodily signals [50,56] | interpretation-directed; protocols adding yoga or medication-use training are mixed | acceptance, catastrophising | second step; order effect predicted |
| Acceptance and commitment therapy | reduced influence of pain on functioning without controlling pain itself [59] | interpretation-directed | acceptance | second step; order effect predicted |
| Education and self-management programmes aimed at beliefs, expectations and self-efficacy | change in self-efficacy and in ways of thinking about headache [1,6] | interpretation-directed | self-efficacy | second step; order effect predicted |
| Biofeedback | regulation of physiological, mental and behavioural responses [63,66] | mixed; uninformative | – | not predicted |
| Relaxation training | regulation of physiological, mental and behavioural responses [63] | mixed; uninformative | – | not predicted |
Table 4.
Applying the classification in clinic.
| Step | Actions | How to judge whether it worked | Caveats |
|---|---|---|---|
| 1. Lower drive: medication overuse | screen for overuse; education and counselling; withdrawal with preventive treatment when education fails; slow tapering for opioids, barbiturates and tranquillisers [37] | acute-medication days below the overuse thresholds [17] | starting preventive treatment with withdrawal favoured reversion to episodic headache in one trial [38] |
| 1. Lower drive: preventive treatment | start or optimise preventive treatment; options for chronic migraine include CGRP-pathway antibodies, atogepant, onabotulinumtoxinA and topiramate [23] | fewer migraine days in the diary after an adequate trial | prescription and reimbursement rules differ between countries; CGRP-pathway antibodies are avoided in pregnancy and lactation [22]; topiramate is avoided in pregnancy and in women of childbearing age without highly effective contraception [23] |
| 1. Lower drive: insomnia | screen for insomnia; behavioural treatment with stimulus control and sleep restriction, digital delivery included [13,42] | insomnia severity, then headache days | evidence on headache outcomes comes from small trials [40,41]; sleep restriction is associated with daytime sleepiness and reduced vigilance during treatment [78] |
| 2. Interpretation-directed treatment | cognitive-behavioural therapy for headache, acceptance and commitment therapy, mindfulness-based interventions, belief-oriented education | self-efficacy, catastrophising and disability first; attack frequency expected to follow mainly once step 1 has worked | offer alongside step 1 when disability or distress is high, when the patient prefers it, when preventive treatment is unavailable, not tolerated or declined, and in pregnancy [23] |
| Graded activity | research setting only | – | no randomised trial in migraine identified; aggravation by routine physical activity is a feature of migraine attacks [17] |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.