
Submitted:
30 September 2026
Posted:
02 October 2026
You are already at the latest version
Abstract
Background: Mumps virus remains an important cause of outbreaks in vaccinated populations despite widespread use of measles–mumps–rubella/varicella (MMR/V) vaccines. Early in 2026, an increase in mumps cases was identified within the Johns Hopkins Health System (JHHS), coinciding with statewide reported cases in the state of Maryland. Methods: Molecular testing was implemented for case confirmation, and positive specimens underwent whole-genome sequencing. Epidemiologic and clinical data were abstracted from medical records. Phylogenetic analysis was performed using complete and partial genomes. Results: Eight patients with laboratory-confirmed mumps infection were identified. The median age was 31 years. Parotitis was the predominant presentation, followed by epididymo-orchitis. Whole-genome sequencing demonstrated that all viruses belonged to mumps virus genotype C and formed a tightly clustered monophyletic lineage with 99.95% nucleotide similarity, consistent with local transmission. Sequences were genetically distinct from genotype G strains reportedly associated with outbreaks in the United States. Comparison with the Jeryl Lynn vaccine strains (genotype A) showed ~7.5% nucleotide divergence. Amino acid analysis of the hemagglutinin-neuraminidase protein identified multiple substitutions in antigenic regions. Conclusions: A genotype C mumps virus cluster was identified during the 2026 Maryland outbreak. Findings are consistent with the introduction and local transmission of an uncommonly reported genotype, supporting the need for widespread molecular diagnostics, and highlighting the value of whole-genome sequencing for outbreak characterization.
Keywords:
mumps virus
; local transmission
; whole‐genome sequencing
1. Introduction
Mumps virus is a highly contagious respiratory pathogen belonging to the genus Orthorubulavirus within the Paramyxoviridae family [1,2]. Despite the widespread implementation of the measles–mumps–rubella/varicella (MMR/V) vaccines, and their marked impact on reducing the disease, mumps outbreaks continue to be reported in the United States (US), including among highly vaccinated populations [3,4,5]. These outbreaks have been associated with waning or suboptimal immune responses to vaccination, close-contact settings, and genotype mismatch with vaccine strains [4,6,7,8].
In February 2026, the Johns Hopkins Health System (JHHS) observed an increase in confirmed and probable mumps cases presenting to JHHS practices, consistent with a statewide rise in reported cases [9]. As of July 16, 2026, the United States reported 129 mumps cases from 23 states, including 50 cases from Maryland (the highest number reported from a single state followed by California, which reported 21 cases), highlighting continued mumps transmission despite high vaccination coverage [9]. This outbreak necessitated the rapid implementation of in-house molecular diagnostic testing for mumps virus. Mumps-positive clinical specimens were subsequently characterized using whole-genome sequencing. This study describes the JHHS response to the 2026 mumps outbreak and the identification of circulating mumps virus genotype C associated with the outbreak.
2. Methods
2.1. Standard of Care Mumps Virus Assay
A real-time PCR assay was developed for the detection of mumps virus in buccal swab specimens on the Panther Fusion platform using the Open Access functionality (validation outline [10]). Primers and probes were based on the CDC Mumps Virus Real-Time RT-PCR Assay (Version 2) protocol [11]. The assay targets the N gene and is inclusive for multiple mumps virus genotypes, including C, H, N, K, G, and A.
2.2. Study Population and Sample Collection
The research was performed with a waiver of consent with an approved IRB protocol, IRB00221396. Clinical Buccal Swab specimens that tested positive for mumps virus were collected following the standard of care testing between February and April 2026. One cerebrospinal fluid (CSF) specimen from a patient who presented with meningoencephalitis and tested positive for mumps virus was also included in the study cohort and characterized by whole-genome sequencing (buccal swab specimen from this patient was not included due to poor genome quality).
Demographic and clinical data from mumps-positive patients were manually collected through review of electronic medical records and laboratory information systems. Variables collected included age, sex, vaccination history, and relevant clinical information, when available.
2.3. Nucleic Acid Extraction and Whole-Genome Sequencing
Viral RNA was extracted from 200 µL of clinical specimens using the QIAamp Viral RNA Mini Kit (Qiagen, Hilden, Germany) according to the manufacturer’s spin-column protocol, with RNA eluted in a final volume of 60 µL. Whole-genome amplification of mumps virus was performed from seven buccal swab specimens and one CSF specimen using the SuperScript III One-Step RT-PCR System with Platinum Taq High Fidelity DNA Polymerase (Thermo Fisher Scientific, Waltham, MA, USA) and previously described primers [12]. Five overlapping long-range amplicons, each approximately 3–4 kb in length, were generated to achieve complete coverage of the mumps virus genome. Amplicons were pooled and purified using NEBNext Sample Purification Beads (NEB) before sequencing. The Native Barcoding (EXP-NBD196) and the NEBNext® ARTIC Library Prep Kits were used for library preparation. Sequencing was performed using the GridION (Oxford Nanopore Technologies) and R10.4.1 flow cells. The resulting FASTQ files were analyzed using a previously described in-house pipeline [13]. Consensus bases were called only at positions with a minimum sequencing depth of 20X; positions with coverage below this threshold were not considered for consensus calling.
2.4. Phylogenetic Analyses
For phylogenetic analysis, five complete and three near-complete (coverage of 68.8% to 84.7%) genome sequences generated in this study were analyzed together with selected reference sequences retrieved from GenBank. Sequence alignments were performed using MAFFT. Maximum-likelihood phylogenetic trees were reconstructed using IQ-TREE3 version 3.0.1 with 1,000 bootstrap replicates, and the best-fit nucleotide substitution model was identified using ModelFinder implemented within IQ-TREE3. Phylogenetic trees were visualized and annotated using custom scripts developed in the R statistical programming environment (version 4.4.1). Genetic distances and nucleotide similarities were calculated using MEGA version 12.
For comparative genomic analyses, the study sequences were compared with the vaccine-associated genotype A Jeryl Lynn strain (JL) [14], using two representative strains JL5 (GenBank accession AF338106) and JL2 (GenBank accession AF345290).
The mumps virus genome sequences generated as a part of this study are publicly available in GenBank under accession numbers PZ803309–PZ803316.
3. Results
3.1. Demographic and Clinical Characteristics of Patients Infected with Mumps
A total of eight patients with confirmed mumps infection were identified among individuals tested between February and April 2026. Patients ranged in age from 23 to 39 years, with a median age of 31 years. Three patients were female (37.5%) (Table 1). Seven cases (87.5%) presented with parotid swelling or bilateral parotitis, which was the most common clinical manifestation. One patient presented with mumps-associated meningitis, while three patients developed testicular swelling and epididymo-orchitis.
Vaccination history was available for several patients, with multiple individuals reporting prior mumps immunization. Most patients did not have documented immuno-compromising conditions.
Most patients resided in Baltimore area, suggesting geographically localized circulation within the region during the study period. Ethnicity data indicated that several patients were identified as Hispanic/Latino.
3.2. Phylogenetic and Sequence Analyses
Phylogenetic analysis of five complete and three near-complete mumps virus genomes demonstrated that the sequences identified in Maryland in 2026 clustered within genotype C and formed a closely related monophyletic cluster, with a nucleotide similarity of 99.95%. This high degree of similarity is consistent with limited genetic diversity and recent local transmission (Figure 1). The Maryland 2026 sequences clustered most closely with genotype C reference strains previously reported from Asia, particularly China and India, as well as with a genotype C strain detected in the Netherlands in 2019.
Overall, the Maryland sequences shared greater than 98.5% nucleotide identity with the genotype C reference strains included in the phylogenetic analysis. The most closely related strain was a genotype C isolate from the Netherlands collected in 2019 (GenBank accession MT238689), which demonstrated approximately 99% nucleotide similarity to the Maryland strains. These findings suggest that the viruses identified in Maryland are more closely related to contemporary internationally reported genotype C strains than to the genotype G strains that have reportedly predominated in the United States.
As expected, the Maryland genotype C viruses were genetically distinct from the vaccine-associated genotype A clade, exhibiting an average nucleotide divergence of 7.5%. The study sequences were also distant from the predominant genotype G strains that have circulated in the United States over the past decade. Consistent with these observations, analysis of publicly available GenBank sequences (accessed May 7, 2026) demonstrated that genotype C viruses have been rarely reported in the United States, with only 16 short genotype C sequences submitted prior to this study.
Comparison of the HN glycoprotein with both Jeryl Lynn vaccine strains (JL5 and JL2) identified 27 amino acid substitutions shared by all Maryland genotype C viruses (Table 2). Several substitutions occurred within previously described antigenic regions, including B-cell epitopes (T120A, N121S, R122K, N123K, V125A, T130I, S351P, and V375I), a reported T-cell epitope (I287V), and predicted HLA-binding regions (R76K and A80I). In addition, N12D is located within a predicted N-linked glycosylation motif [15,16,17]. These findings highlight the genetic divergence of the Maryland genotype C viruses from the vaccine genotype A strains. Comparison of the glycoprotein of our strains with closely related strain from Asia showed highly similar amino acid profiles, with only three differences identified (A80I, F314Y, and S368N). In addition to variation within the HN glycoprotein, comparison of the fusion (F) glycoprotein with both Jeryl Lynn vaccine components (JL5 and JL2) identified six amino acid substitutions shared by all Maryland genotype C viruses relative to both vaccine strains (I13F, I405V, I498M, I7T, P5L, and R318S). Additional substitutions were observed relative to JL2 only (A489T, K2R, S326L, S480N, V275I, and Y4F) or JL5 only (F477V, G480N, L95P, M331I, N2R, S177N, S489T, T24I, T431A, and Y11F). None of the observed F protein substitutions mapped to previously described major antigenic or immune-recognition regions, and their biological significance remains unknown. Nevertheless, these findings further demonstrate the genetic divergence of the Maryland genotype C viruses from the genotype A Jeryl Lynn vaccine strains.
4. Discussion
In this study, we describe the detection and genomic characterization of a cluster of mumps virus genotype C identified from patients with confirmed mumps infections at JHHS in early 2026. To date, multiple mumps virus genotypes have been identified based on sequence diversity within the small hydrophobic (SH) gene, with genotype G being the predominant genotype reported from the US and many other countries over the past two decades [18,19,20]. Genotype C has been reported less frequently, primarily from parts of Asia, with only sporadic reports elsewhere [20,21]. To our knowledge, genotype C has been rarely reported from the US, making this outbreak one of a few documented clusters characterized using whole-genome sequencing. Our findings highlight the value of genomic surveillance for monitoring changes in mumps virus circulation patterns [20].
The introduction of the live attenuated mumps vaccine and the subsequent implementation of a two-dose measles–mumps–rubella (MMR) vaccination schedule led to a dramatic decline in mumps incidence in the US, reducing reported cases by more than 99% compared with the pre-vaccine era [22]. However, mumps outbreaks continue to occur among highly vaccinated populations, particularly adolescents and young adults in close-contact settings such as universities and military environments [6,7,23,24]. This epidemiologic shift from predominantly pediatric disease to outbreaks among vaccinated young adults has been attributed largely to waning immunity several years after vaccination [25,26]. In addition, genetic and antigenic differences between the vaccine-associated genotype A strain and circulating genotypes have been investigated as potential contributors to breakthrough infections and reduced neutralization efficiency [5,15,19,27,28]. Although mumps virus remains serologically monotypic, accumulating evidence suggests that variation within key antigenic regions of the HN and F glycoproteins may influence vaccine-induced immune responses [15,27,29,30]
The continued occurrence of mumps outbreaks among highly vaccinated populations has prompted reconsideration of current vaccination strategies. The Advisory Committee on Immunization Practices (ACIP) recommends a third dose of MMR vaccine for individuals at increased risk during mumps outbreaks, as studies have demonstrated additional protection and reduced transmission in outbreak settings [6,31]. However, questions remain regarding the durability of this protection and whether future vaccination strategies may need to consider periodic booster doses or updated vaccine formulations which could better reflect the genetic diversity of currently circulating mumps virus genotypes [15,26].
Clinical manifestations of mumps range from asymptomatic or mild respiratory illness and parotitis to severe complications such as orchitis, meningitis, encephalitis, pancreatitis, and hearing loss [22]. Patients who had confirmed mumps infections at JHHS presented with classic clinical signs of mumps, including parotitis. One patient presented with suspected mumps-associated meningitis and three patients experienced testicular complications, including orchitis or epididymo-orchitis. With the association of other viral infections with parotitis (e.g., influenza, enterovirus, and human parainfluenza virus) and the changes in disease incidence following vaccine introduction, the diagnosis of mumps virus infection has become largely laboratory-based. Limitations of serologic testing in vaccinated populations highlight the importance of molecular methods as the current gold standard for case confirmation. Expansion of testing facilitates rapid case identification, isolation, and early outbreak containment. Implementing a laboratory-developed test to serve JHHS patients has been of utmost importance in responding to the current Maryland outbreak.
Phylogenetic analysis demonstrated that all Maryland sequences clustered within genotype C and formed a highly supported monophyletic cluster with an average nucleotide similarity of 99.95%. The limited genetic diversity observed among the study sequences suggests a recent common ancestor and is consistent with local transmission. Although epidemiological links between cases could not be established, the close genetic relatedness of the viruses and the geographic proximity of the patients support circulation within the local community rather than multiple independent introductions [21].
The Maryland genotype C viruses were most closely related to strains previously reported from Asia, particularly China and India, and to a genotype C virus detected in the Netherlands in 2019. These findings are consistent with previous reports demonstrating the global circulation of genotype C viruses and the international movement of mumps virus through travel and population mobility [20,21]. Phylogenetic relationships suggest that the Maryland viruses belong to a contemporary globally circulating genotype C rather than representing a long-standing endemic U.S. clade.
The Maryland genotype C viruses were also genetically distinct from the vaccine-associated genotype A, exhibiting an average nucleotide divergence of 7.5%. Previous studies have demonstrated genetic and antigenic differences between the Jeryl Lynn vaccine strains and contemporary circulating mumps virus genotypes, including genotypes G and H, although the currently licensed MMR vaccine continues to provide protection against severe disease and complications [5,8]. The occurrence of infections among individuals with reported prior vaccination is consistent with previous observations that mumps outbreaks can occur in vaccinated populations, likely reflecting a combination of waning immunity and continued viral transmission in close-contact settings [6,22].
Comparative analysis of the HN glycoprotein revealed substantial amino acid divergence between the Maryland genotype C viruses and the genotype A Jeryl Lynn vaccine strains. Several substitutions were located within previously described antigenic regions, including B-cell epitopes, a reported T-cell epitope, and predicted HLA-binding regions, suggesting that the circulating genotype C viruses possess distinct antigenic characteristics compared with the vaccine strain [15,16]. In addition, the N12D substitution was located within a predicted N-linked glycosylation motif, a feature that may influence glycoprotein structure and antigen presentation. Although the functional consequences of these substitutions remain unknown, their occurrence within immune-relevant regions is consistent with previous studies demonstrating genetic and antigenic differences between vaccine-associated genotype A viruses and contemporary circulating mumps virus genotypes [5,16,32]. Importantly, mumps virus remains serologically monotypic, and current evidence indicates that the MMR vaccine continues to provide protection against severe disease and complications despite genetic variation among circulating strains [5]
In conclusion, this study documents the detection and genomic characterization of a rarely reported genotype C mumps virus cluster identified within JHHS during the 2026 Maryland mumps outbreak. Phylogenetic analysis demonstrated that the Maryland viruses formed a closely related monophyletic cluster within a contemporary, globally circulating genotype C lineage and were genetically distinct from the genotype A Jeryl Lynn vaccine strains. Comparative analysis of the HN glycoprotein identified multiple substitutions within previously described antigenic regions, highlighting the genetic divergence of the circulating genotype C viruses from the vaccine strain. These findings underscore the value of integrating molecular diagnostics and whole-genome sequencing into routine surveillance to monitor changes in mumps virus circulation and detect the introduction of uncommon genotypes.:
Funding
This work was supported in part by HHS 75N93021C00045.
Conflicts of Interest
H. H. M. collaborates for research with Hologic, Qiagen, and Diasorin. H. H. M. received honoraria from Roche Diagnostics, Qiagen, Diasorin, bioMérieux, and BD Diagnostics. All other authors report no potential conflicts.
References
- Jin, L.; Orvell, C.; Myers, R.; Rota, P.A.; Nakayama, T.; Forcic, D.; Hiebert, J.; Brown, K.E. Genomic diversity of mumps virus and global distribution of the 12 genotypes. Rev. Med. Virol. 2015, 25, 85–101. [Google Scholar] [CrossRef]
- Wielders, C.C.; van Binnendijk, R.S.; Snijders, B.E.; Tipples, G.A.; Cremer, J.; Fanoy, E.; Dolman, S.; Ruijs, W.; Boot, H.J.; de Melker, H.E.; et al. Mumps epidemic in orthodox religious low-vaccination communities in the Netherlands and Canada, 2007 to 2009. Euro Surveill. 2011, 16. [Google Scholar] [CrossRef]
- Hiebert, J.; Saboui, M.; Frost, J.R.; Zubach, V.; Laverty, M.; Severini, A. Mumps resurgence in a highly vaccinated population: Insights gained from surveillance in Canada, 2002-2020. Vaccine 2023, 41, 3728–3739. [Google Scholar] [CrossRef]
- Rubin, S.; Kennedy, R.; Poland, G. Emerging Mumps Infection. Pediatr. Infect. Dis. J. 2016, 35, 799–801. [Google Scholar] [CrossRef]
- Rubin, S.A.; Link, M.A.; Sauder, C.J.; Zhang, C.; Ngo, L.; Rima, B.K.; Duprex, W.P. Recent mumps outbreaks in vaccinated populations: No evidence of immune escape. J. Virol. 2012, 86, 615–620. [Google Scholar] [CrossRef]
- Cardemil, C.V.; Dahl, R.M.; James, L.; Wannemuehler, K.; Gary, H.E.; Shah, M.; Marin, M.; Riley, J.; Feikin, D.R.; Patel, M.; et al. Effectiveness of a Third Dose of MMR Vaccine for Mumps Outbreak Control. N Engl. J. Med. 2017, 377, 947–956. [Google Scholar] [CrossRef]
- Guo, A.; Leung, J.; Ayers, T.; Fields, V.S.; Safi, H.; Waters, C.; Curns, A.T.; Routh, J.A.; Haselow, D.T.; Marlow, M.A.; et al. Mumps vaccine effectiveness of a 3rd dose of measles, mumps, rubella vaccine in school settings during a mumps outbreak -- Arkansas, 2016-2017. Public Health Pract. 2023, 6, 100404. [Google Scholar] [CrossRef]
- Risalvato, J. Mumps Virus: Replication, Immune Response, and the Changing Landscape of Vaccine Effectiveness. Pathogens 2026, 15. [Google Scholar] [CrossRef]
- Available online: https://www.cdc.gov/mumps/outbreaks/index.html.
- Jarrett, J.; Hanlon, A.; Klein, E.; Mostafa, H.H. Automating laboratory developed tests using the panther fusion open access: Analytical and clinical evaluation of assays for the detection of viral causes of meningitis and encephalitis. J. Clin. Virol. 2026, 185, 105968. [Google Scholar] [CrossRef]
- Available online: https://www.cdc.gov/mumps/downloads/simple-protocol-MuV-rRT-PCR.pdf.
- Stapleton, P.J.; Eshaghi, A.; Seo, C.Y.; Wilson, S.; Harris, T.; Deeks, S.L.; Bolotin, S.; Goneau, L.W.; Gubbay, J.B.; Patel, S.N. Evaluating the use of whole genome sequencing for the investigation of a large mumps outbreak in Ontario, Canada. Sci. Rep. 2019, 9, 12615. [Google Scholar] [CrossRef]
- Fall, A.; Morris, C.P.; Elgazayerly, O.; Wu, A.; Abdullah, O.; Norton, J.M.; Pekosz, A.; Klein, E.; Mostafa, H.H. Emergence and Circulation of a Recombinant Enterovirus D68 Identified by Genomic Surveillance; The Johns Hopkins Health System, Maryland, 2025. [Google Scholar] [CrossRef]
- Marlow, M.; Haber, P.; Hickman, C.; Patel, M. Epidemiology and Prevention of Vaccine-Preventable Diseases. Chapter 15: Mumps. 2021. Available online: https://www.cdc.gov/pinkbook/hcp/table-of-contents/chapter-15-mumps.html?utm_source.
- Gouma, S.; Vermeire, T.; Van Gucht, S.; Martens, L.; Hutse, V.; Cremer, J.; Rota, P.A.; Leroux-Roels, G.; Koopmans, M.; van Binnendijk, R.; et al. Differences in antigenic sites and other functional regions between genotype A and G mumps virus surface proteins. Sci. Rep. 2018, 8, 13337. [Google Scholar] [CrossRef]
- Frost, J.R.; Severini, A. Complete Genome Sequence of the World Health Organization Mumps Reference Strain, MuVi/Sheffield.GBR/1.05. Microbiol. Resour. Announc 2022, 11, e0033622. [Google Scholar] [CrossRef]
- Frost, J.R.; Shaikh, S.; Severini, A. Exploring the Mumps Virus Glycoproteins: A Review. Viruses 2022, 14. [Google Scholar] [CrossRef]
- McNall, R.J.; Wharton, A.K.; Anderson, R.; Clemmons, N.; Lopareva, E.N.; Gonzalez, C.; Espinosa, A.; Probert, W.S.; Hacker, J.K.; Liu, G.; et al. Genetic characterization of mumps viruses associated with the resurgence of mumps in the United States: 2015-2017. Virus Res. 2020, 281, 197935. [Google Scholar] [CrossRef]
- Bryant, P.; Caldwell, H.; Lamson, D.M.; Yildirim, T.; St George, K. Streamlined Whole-Genome Sequencing of Mumps Virus for High-Resolution Outbreak Analysis. J. Clin. Microbiol. 2022, 60, e0084121. [Google Scholar] [CrossRef]
- Jin, L.; Rima, B.; Brown, D.; Orvell, C.; Tecle, T.; Afzal, M.; Uchida, K.; Nakayama, T.; Song, J.W.; Kang, C.; et al. Proposal for genetic characterisation of wild-type mumps strains: Preliminary standardisation of the nomenclature. Arch. Virol. 2005, 150, 1903–1909. [Google Scholar] [CrossRef]
- Cui, A.; Zhu, Z.; Hu, Y.; Deng, X.; Sun, Z.; Zhang, Y.; Mao, N.; Xu, S.; Fang, X.; Gao, H.; et al. Mumps Epidemiology and Mumps Virus Genotypes Circulating in Mainland China during 2013-2015. PLoS ONE 2017, 12, e0169561. [Google Scholar] [CrossRef]
- Hviid, A.; Rubin, S.; Muhlemann, K. Mumps. Lancet 2008, 371, 932–944. [Google Scholar]
- Ramanathan, R.; Voigt, E.A.; Kennedy, R.B.; Poland, G.A. Knowledge gaps persist and hinder progress in eliminating mumps. Vaccine 2018, 36, 3721–3726. [Google Scholar] [CrossRef]
- Dayan, G.H.; Rubin, S. Mumps outbreaks in vaccinated populations: Are available mumps vaccines effective enough to prevent outbreaks? Clin. Infect. Dis. 2008, 47, 1458–1467. [Google Scholar] [CrossRef]
- Connell, A.R.; Connell, J.; Leahy, T.R.; Hassan, J. Mumps Outbreaks in Vaccinated Populations-Is It Time to Re-assess the Clinical Efficacy of Vaccines? Front Immunol. 2020, 11, 2089. [Google Scholar] [CrossRef]
- Lewnard, J.A.; Grad, Y.H. Vaccine waning and mumps re-emergence in the United States. Sci. Transl. Med. 2018, 10. [Google Scholar] [CrossRef]
- Gouma, S.; Ten Hulscher, H.I.; Schurink-van ‘t Klooster, T.M.; de Melker, H.E.; Boland, G.J.; Kaaijk, P.; van Els, C.; Koopmans, M.P.G.; van Binnendijk, R.S. Mumps-specific cross-neutralization by MMR vaccine-induced antibodies predicts protection against mumps virus infection. Vaccine 2016, 34, 4166–4171. [Google Scholar] [CrossRef]
- Rasheed, M.A.U.; Hickman, C.J.; McGrew, M.; Sowers, S.B.; Mercader, S.; Hopkins, A.; Grimes, V.; Yu, T.; Wrammert, J.; Mulligan, M.J.; et al. Decreased humoral immunity to mumps in young adults immunized with MMR vaccine in childhood. Proc. Natl. Acad. Sci. U S A 2019, 116, 19071–19076. [Google Scholar] [CrossRef]
- Alkam, D.; Jenjaroenpun, P.; Wongsurawat, T.; Udaondo, Z.; Patumcharoenpol, P.; Robeson, M.; Haselow, D.; Mason, W.; Nookaew, I.; Ussery, D.; et al. Genomic characterization of mumps viruses from a large-scale mumps outbreak in Arkansas, 2016. Infect. Genet Evol. 2019, 75, 103965. [Google Scholar] [CrossRef]
- Vermeire, T.; Barbezange, C.; Francart, A.; Hamouda, A.; Litzroth, A.; Hutse, V.; Martens, L.; Vandermarliere, E.; Van Gucht, S. Sera from different age cohorts in Belgium show limited cross-neutralization between the mumps vaccine and outbreak strains. Clin. Microbiol. Infect. 2019, 25, 907 e1–907 e6. [Google Scholar] [CrossRef]
- Marin, M.; Marlow, M.; Moore, K.L.; Patel, M. Recommendation of the Advisory Committee on Immunization Practices for Use of a Third Dose of Mumps Virus-Containing Vaccine in Persons at Increased Risk for Mumps During an Outbreak. MMWR Morb. Mortal. Wkly. Rep. 2018, 67, 33–38. [Google Scholar] [CrossRef]
- Ivancic, J.; Gulija, T.K.; Forcic, D.; Baricevic, M.; Jug, R.; Mesko-Prejac, M.; Mazuran, R. Genetic characterization of L-Zagreb mumps vaccine strain. Virus Res. 2005, 109, 95–105. [Google Scholar] [CrossRef]
- Kaaijk, P.; Emmelot, M.E.; Kerkhof, J.; van Els, C.; Meiring, H.D.; de Wit, J.; Bodewes, R. Genetic Analysis Reveals Differences in CD8(+) T Cell Epitope Regions That May Impact Cross-Reactivity of Vaccine-Induced T Cells against Wild-Type Mumps Viruses. Vaccines 2021, 9. [Google Scholar] [CrossRef]
Figure 1.
Phylogenetic analysis of mumps viruses characterized from the Johns Hopkins Health System, February- April 2026. Complete and near-complete genome sequences generated in this study were analyzed with publicly available global reference sequences for contextual comparison. The maximum-likelihood phylogenetic tree was reconstructed using IQ-TREE2 with 1,000 bootstrap replicates. Bootstrap support values ≥90 are indicated by black dots at the corresponding nodes.
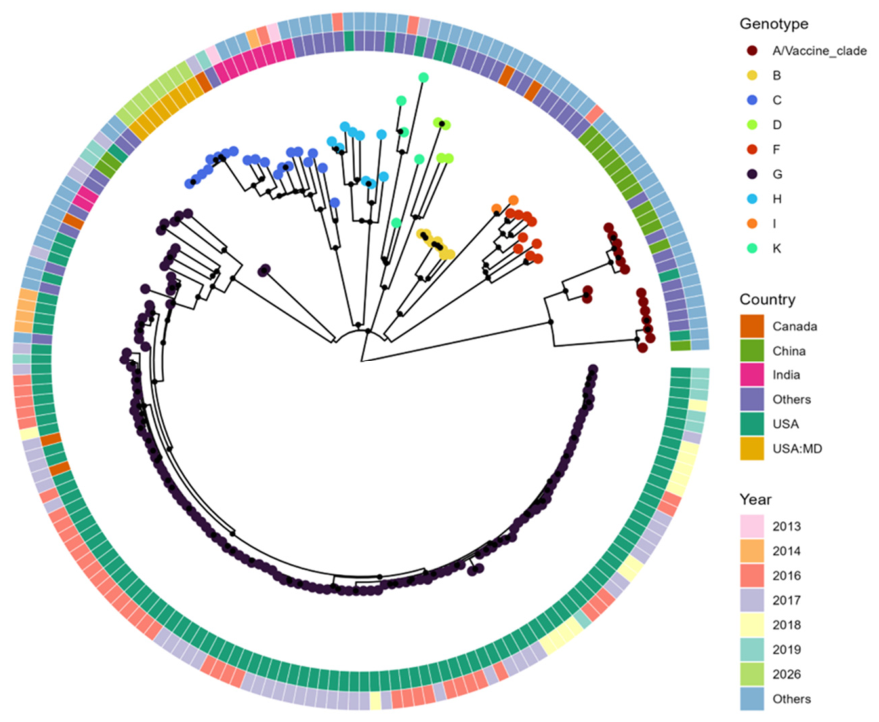

Table 1.
Demographic and Clinical Characteristics of patients with confirmed mumps, February to April 2026.
Table 1.
Demographic and Clinical Characteristics of patients with confirmed mumps, February to April 2026.
| Positive-Mumps | |
|---|---|
| Total | 8 |
| Female (%) | 3 (37.5) |
| Median age (IQR)—yr | 31 (25-36) |
| Race/Ethnicity (%) | |
| Hispanic | 7 (87.5) |
| White | 1 (12.5) |
| Clinical signs (%) | |
| Parotid swelling | 7 (87.5) |
| Epididymo-orchitis/ Testicular swelling | 3 (37.5) |
| Meningitis | 1 (12.5) |
| Immunization Status (%) | |
| Vaccinated | 4 (50) |
| Unvaccinated | 3 (37.5) |
| Unsure | 1 (12.5) |
Table 2.
Amino acid substitutions identified in the HN and F glycoproteins of Maryland genotype C mumps viruses relative to the Jeryl Lynn vaccine strains JL5 and JL2.
Table 2.
Amino acid substitutions identified in the HN and F glycoproteins of Maryland genotype C mumps viruses relative to the Jeryl Lynn vaccine strains JL5 and JL2.
| Protein | Potential Effect | Amino Acid Substitution | Reference |
|---|---|---|---|
| HN | N-linked glycosylation: Predicted disruption of an N-linked glycosylation motif; located adjacent to antigenic regions | N12D | [15,16] |
| HN | T-cell epitope / HLA-binding region: Predicted reduction in HLA binding affinity and potential alteration of T-cell recognition | R76K, A80I, I287V | [15,16] |
| HN | B-cell epitopes: Located within previously described antigenic regions; may influence antibody recognition | T120A, N121S, R122K, N123K, V125A, T130I, S351P, V375I |
[15,16,33] |
| HN | Other substitutions | I8T, M9I, V20G, V21I, G25N, I56V, T275I, S295T, F314Y, E356D, S368N, S372N, V396I, V474A, A577T | |
| F | Other substitutions | I7T, P5L, I13F, R318S, I405V, I498M | |
| F | Changes relative to JL2 | A489T, K2R, S326L, S480N, V275I, Y4F | |
| F | Changes relative to JL5 | F477V, G480N, L95P, M331I, N2R, S177N, S489T, T24I, T431A, Y11F |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.