

Submitted:
29 September 2026
Posted:
01 October 2026
You are already at the latest version
Abstract
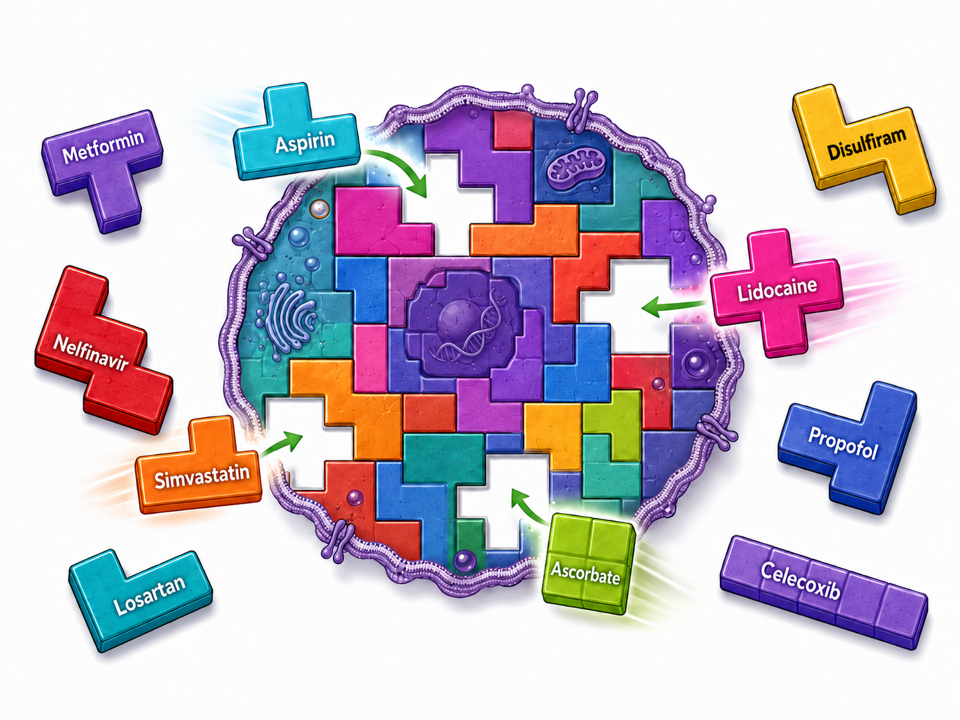
Drug repurposing builds on pharmacological and safety information already available for an approved drug, but this advantage requires additional studies to establish the biological effect and related mechanisms of action. We conducted a clinically focused review of non-oncology drugs tested as active cancer treatments in interventional studies from 1 January 2021 to 31 July 2026. Randomized trials, phase II-III studies, biomarker-selected cohorts, and studies reporting pharmacokinetics or human target engagement were prioritized. Despite the large number of registered studies, the landscape is still dominated by early-phase, academically sponsored trials. Several widely studied candidates, including metformin, nelfinavir, disulfiram-copper, losartan, and propofol, were negative in randomized evaluations. Conversely, aspirin reduced recurrence in localised colorectal cancer with alterations in the PI3K gene, whilst pre-operative administration of peritumoural lidocaine was associated with improved disease-free survival and overall survival in a randomised trial of breast cancer. Pharmacological insights related to ascorbate in pancreatic cancer and simvastatin in recurrent small-cell lung cancer yielded promising results. Across drug classes, unsuccessful programs were often limited by inadequate exposure, uncertain tumor penetration, absent pharmacodynamic evidence, heterogeneous patient populations, or weak continuity between exploratory and confirmatory development. Progress will depend on more selective clinical hypotheses, early demonstration of human pharmacology, prospective biomarkers, and clear regulatory ownership.
Keywords:
drug repurposing
; oncology
; clinical trials
; biomarkers
; pharmacokinetics
; off-label use
; precision repurposing
1. Introduction
Cancer treatment has changed markedly with molecular classification, targeted agents, antibody–drug conjugates, and immunotherapy, yet the global burden of disease continues to rise [1,2,3,4,5,6]. Resistance remains a common problem, access to new treatments is uneven, and the cost and complexity of modern systemic therapy are substantial. These pressures explain the continuing interest in finding anticancer uses for drugs that are already available [7,8,9,10]. Drug repurposing, also known as repositioning, involves developing an existing drug for a new therapeutic use [7,8]. Here, we use a deliberately narrow definition: the drug must have been developed and authorized for a non-oncological condition and must subsequently have been tested with a direct antitumor purpose. Supportive care and the use of an established anticancer drug in another tumor type were not included. Additionally, we also distinguish repurposing from off-label prescribing as off-label use refers to clinical practice outside the approved label, whereas repurposing represents an evidence-generating process intended to establish a new therapeutic role.
Thalidomide provides a historical example of successful, but highly context-dependent, drug repurposing. Introduced in Europe in the late 1950s as a sedative and an antiemetic during pregnancy, it was withdrawn from the market in the early 1960s due to its association with severe congenital malformations. Subsequent studies have highlighted the anti-inflammatory, immunomodulatory, and antiangiogenic effects of thalidomide, demonstrating clinically relevant activity in multiple myeloma, whereas results in solid tumors were inconsistent. Experimental studies linked its biological activity to the inhibition of angiogenic signaling pathways such as basic fibroblast growth factor and vascular endothelial growth factor, as well as to modulation of tumor necrosis factor-α, nuclear factor-κB, adhesion molecules, and T-cell responses [11,12,13,14,15,16]. These findings provided the rationale for reconsidering thalidomide, previously known primarily for its severe teratogenetic effect, as a potential treatment for immune-mediated diseases and cancer [17]. The most important oncological development occurred in multiple myeloma. Early clinical studies demonstrated activity in heavily pretreated and refractory disease, initially with single-agent thalidomide and subsequently with combinations containing dexamethasone or cytotoxic drugs [18,19,20,21]. The 2004 review by Eleutherakis-Papaiakovou and colleagues reported responses in approximately one-third of patients treated with thalidomide as monotherapy and higher response rates when it was combined with dexamethasone, although the early evidence also highlighted uncertainty regarding optimal dosing and the additional contribution of each component of multidrug regimens. Activity in solid tumors was considerably less consistent, with limited or modest signals reported in prostate cancer, renal-cell carcinoma, melanoma, Kaposi’s sarcoma, and high-grade glioma, whereas other tumor types showed little or no benefit [17]. Thalidomide is now used in its racemic form as an antimyeloma agent, generally in combination regimens rather than as an isolated treatment. Current clinical-trial information describes its use with dexamethasone, melphalan and prednisone, or combinations incorporating bortezomib and cyclophosphamide, while additional studies continue to investigate thalidomide-containing regimens in multiple myeloma and other selected malignancies. Its anticancer role therefore represents a genuine transition from a non-oncological sedative to an established component of cancer therapy [7], thanks to the recognition of a disease in which the drug’s immunomodulatory and microenvironmental actions were clinically relevant. However, the same adverse effects that complicated early development remain clinically important. Thalidomide is highly teratogenic and can also cause peripheral neuropathy, sedation, constipation, cutaneous reactions, and venous thromboembolism, particularly in combination regimens with corticosteroids or chemotherapy. Its contemporary use is consequently inseparable from pregnancy-prevention programs, neurological monitoring, thrombotic-risk assessment, and careful selection of accompanying treatments. The thalidomide case illustrates both the promise and the limitations of repurposing. A drug abandoned because of catastrophic toxicity was eventually shown to have substantial activity in a specific hematological malignancy, although its known safety profile did not eliminate the need for oncology-specific risk assessment. It also shows that successful repurposing may completely transform the clinical identity of a drug, turning a non-oncology compound into an established anticancer agent [17,22].
Existing drugs offer a useful starting point because their manufacture, human pharmacokinetics, adverse effects and major interactions are often well described. Many are generic or off patent, which could make effective treatment widely accessible. Even so, oncology may require a different dose, formulation, route, duration, or combination from the original indication. [7,8,9]. Moreover, previous clinical experience does not ensure that toxicity will remain acceptable in oncological patients, who may receive prolonged multidrug treatment and have organ dysfunction, cytopenias, or additional thrombotic and neurological risk factors.
The recent clinical record has exposed the limitations of broad, empirically driven repurposing strategies. Several widely studied candidates have failed to improve meaningful outcomes in unselected patient populations, whereas more convincing signals have emerged in biologically defined subgroups or in narrowly specified treatment settings. Accordingly, this review does not aim to catalogue all registered repurposing trials. Instead, it focuses on the most clinically informative human interventional studies conducted in the last five years, including positive, negative, and inconclusive results. Particular emphasis is placed on the factors that determine whether a promising non-oncology drug can advance toward clinical translation, including clinically achievable exposure, evidence of tumor target engagement, prospective biomarker selection, randomized validation, and the regulatory pathway required to transform an off-label hypothesis into an established anticancer indication.
2. Literature Search, Definitions and Selection
This narrative review was designed to identify clinically informative trials prioritizing studies that could clarify efficacy, pharmacological feasibility, biomarker dependence, mechanisms of failure, or prospects for clinical translation.
We searched PubMed/MEDLINE, ClinicalTrials.gov, the WHO International Clinical Trials Registry Platform, CTIS/EudraCT, and the Repurposing Drugs in Oncology (ReDO) database. Search queries related to drug repurposing, cancer, and clinical trials, were combined with the names of individual drugs identified from recent reviews, trial registries, and reference lists. The final literature and registry search were closed on 31 July 2026.
Eligible studies were phase I-III interventional trials in patients with malignant disease in which a drug originally approved outside oncology was assigned for a direct antitumor purpose. We considered monotherapy and combination studies, including therapeutic window adjuvant, maintenance, and perioperative designs. Randomized trials, phase II-III programs, biomarker-selected cohorts, and studies reporting clinical outcomes or human target engagement were prioritized.
Preclinical and observational reports were used only when they clarified a trial’s rationale or design. We excluded studies limited to symptom control, prevention of treatment toxicity, management of comorbidity, or primary cancer prevention. Ongoing trials were included selectively when they represented an important confirmatory program. As this was a comprehensive review, selection was therefore focused on clinical informativeness rather than on exhaustive inclusion.
3. Current Analysis of Clinical Landscape
The ReDO database offers a useful snapshot of active interventional studies in which licensed non-cancer drugs are being tested as anticancer treatments. Its 2021 analysis identified 805 active trials involving 164 drugs, equivalent to roughly 5% of active interventional oncology studies. Most were phase II, only one out of ten were phase III, 87% developed within academy, and more than 80% of the drugs were off patent. On 23 April 2026, the live database listed 1,045 active trials involving 198 drugs [23]. Since completed and discontinued trials are not included in the database, these values are snapshots of the active pipeline rather than a cumulative count.
A relatively small group of familiar drugs accounts for much of this activity, notably metformin, celecoxib, hydroxychloroquine (HCQ), aspirin, ascorbate, propranolol, propofol, valproic acid, and statins. More than half of active studies are uncontrolled, and pediatric trials remain uncommon. The scale of the pipeline therefore overstates the maturity of the evidence: many studies examine the same drug in different tumors without a common biomarker strategy, dose rationale, or route to confirmation.
We judged the evidence by the quality of the clinical question rather than by the number of registered studies. The most informative programs combined a plausible human exposure with evidence of tumor or microenvironmental target engagement, a biologically defined population, an appropriate comparator, and a clinically meaningful endpoint. The trials that most strongly influenced our assessment are summarized in Table 1.
4. Clinical Evidence Across Pharmacological Classes
4.1. Metabolic, Cardiovascular and Anti-Inflammatory Drugs
Metformin is the most frequently studied repurposing candidate, but recent randomized trials have been consistently disappointing. The MA.32 randomized clinical trial found no improvement in invasive disease-free or overall survival among non-diabetic patients at high risk of breast cancer [24]. The multicenter, phase III, double-blind, placebo-controlled trial involved 3,649 non-diabetic patients with high-risk, non-metastatic breast cancer who were receiving standard treatment. Participants were randomly assigned to receive either metformin at a dose of 850 mg twice daily or placebo for five years. The primary study looked at patients with hormone receptor-positive disease. After a middle follow-up of approximately eight years, metformin did not improve invasive disease-free survival in the hormone receptor-positive population with a similar incidence of invasive disease-free survival events between the metformin-treated group and the placebo-treated group (hazard ratio 1.01). No significant improvement was observed in global survival, distant recurrence-free survival or breast cancer-free interval. A benefit was also not demonstrated in the hormone receptor-negative cohort, for which futility had previously been declared. Non-hematological grade 3 adverse events were more frequent with metformin, largely reflecting its gastrointestinal toxicity. The MA.32 results substantially weakened the rationale for administering metformin routinely to non-diabetic patients with early-stage breast cancer and showed that epidemiological associations between metformin exposure and favorable cancer outcomes cannot be assumed. Nevertheless, the trial does not exclude the possibility that metformin could benefit biologically selected subgroups. Exploratory analyses and smaller therapeutic window studies have suggested that systemic metabolic status, insulin concentrations, body mass index, tumor subtype, and specific molecular alterations may influence treatment response. These hypotheses remain insufficient for clinical implementation and require prospective validation [24].
Randomized studies on ovarian cancer, low-risk prostate cancer under active surveillance, and hormone-sensitive metastatic prostate cancer were also negative in their overall populations [25,26,27]. In a phase II, randomized, double-blind, placebo-controlled clinical trial, 108 evaluable patients with newly diagnosed advanced ovarian cancer received first-line platinum- and taxane-based chemotherapy, in combination with metformin at a dose of 850 mg twice daily or with placebo [25]. Both treatments were subsequently continued as maintenance therapy for up to two years, revealing that the additional use of metformin did not significantly increase progression-free survival, with a median progression-free survival values of 15.4 months in the metformin group and 14.3 months in the placebo group (hazard ratio 0.87). Overall survival also showed no improvement, with medians of 40.7 and 43.8, months respectively. The combination was generally well tolerated, but the absence of an efficacy advantage did not support further use of metformin in an unselected population with newly diagnosed advanced ovarian cancer. These findings are of particular relevance because ovarian cancer has been considered a plausible setting for metabolic intervention, also due to associations with obesity, insulin resistance, lipid metabolism, and tumor progression. The negative randomized evidence indicates that such associations do not support the addition of metformin to standard platinum-based treatment without a predictive biomarker [25]
Two major randomized trials reported during the selected period further clarified the role of metformin in prostate cancer [26,27]. The Metformin Active Surveillance Trial was a multicenter, double-blind, placebo-controlled, phase III trial enrolling 408 men with low-risk localized prostate cancer who were being managed by active surveillance. Participants were given metformin, 850 mg twice daily, or a placebo, and were monitored for up to 36 months. Metformin did not delay pathological or therapeutic progression compared with placebo. The overall risk ratio for disease progression was 1.11, and the difference was not statistically significant. Moreover, a predefined analysis according to body mass index identified an increased risk of pathological progression among participants with obesity who received metformin. Although this subgroup results requires cautious interpretation, not assuming that patients with greater metabolic dysfunction necessarily have greater anticancer benefit [26]. The evaluation of metformin as part of the STAMPEDE study (Systemic Therapy in Advancing or Metastatic Prostate Cancer: Evaluation of Drug Efficacy), a large-scale clinical research platform established to test new treatments and therapeutic combinations, has provided an even broader assessment of metformin in hormone-sensitive metastatic prostate cancer. A total of 1,874 non-diabetic patients who had started androgen deprivation therapy were randomly assigned to receive either standard treatment (ADT in combination with radiotherapy, docetaxel or ARPI) alone, or standard treatment combined with metformin, 850 mg twice daily. An analysis of the results of a prospective randomized trial showed that Metformin does not significantly improve overall survival in the intention-to-treat population. The median overall survival was 67.4 months with metformin and 61.8 months with standard therapy alone, corresponding to a risk ratio of 0.91. A subgroup analysis suggested a possible beneficial effect on overall-survival in patients with high-volume metastatic disease, with a risk ratio of approximately 0.79, whilst no benefit was observed in patients with low-volume disease. This finding does not establish metformin as a treatment for high-volume prostate cancer, considering that the overall trial endpoint was negative, and the interaction requires further biological and clinical validation. Metformin, however, reduced several adverse metabolic consequences of androgen-deprivation therapy, including unfavorable changes in body weight and lipid parameters. In this setting, its metabolic effects may ultimately be more clinically reproducible than its direct anticancer activity [27].
The cumulative evidence available by 31 July 2026 does not justify the routine addition of metformin to cancer treatment in patients without diabetes. Randomized trials, including large phase III studies, have failed to demonstrate meaningful benefits in early breast cancer, advanced ovarian cancer, low-risk prostate cancer under active surveillance, and the general population with hormone-sensitive metastatic prostate cancer [24,25,26,27] Future investigation should therefore move away from broadly inclusive trials based only on tumor type. More informative approaches would include patients selected according to hyperinsulinemia, insulin resistance, expression of metformin transporters, or molecular alterations associated with energetic stress leading also to tumor dependence on oxidative phosphorylation. Pharmacodynamic evidence of target engagement should also be obtained before starting large efficacy trials. The possible survival signal in high-volume metastatic prostate cancer illustrates the importance of defining disease contexts in which metabolic intervention may be more relevant, but it is currently insufficient to change clinical practice.
The clinical evidence for statins remains less established. In a phase II, single-center, open-label study, 40 patients with recurrent small-cell lung cancer (SCLC) were randomized to receive nab-paclitaxel as monotherapy or in combination with simvastatin 20 mg/day; 32 patients were included in the efficacy analysis [28]. The addition of simvastatin greatly increased the disease control rate from 44.4% to 92.9% and the objective response rate from 11.1% to 50.0%. Median progression-free survival was also extended from 62 to 113 days (HR 0.42; 95% CI 0.19-0.92; P=0.029). However, the median overall survival was similar between the two groups (208 versus 204 days; HR 0.76; P=0.504). Toxicity remained manageable, with no meaningful increase in treatment-related adverse events, creatine-kinase elevation, or statin-associated myopathy. Exploratory analyses of baseline GGPS1 (geranylgeranyl diphosphate synthase 1) expression suggested that simvastatin might counteract mevalonate-pathway-mediated chemotherapy resistance, although tumor samples were available from only eight patients and no statistically significant biomarker interaction was demonstrated. These outcomes confirm the need for further investigation into simvastatin as a chemotherapy sensitizer, but the small sample size, single-center design, incomplete efficacy evaluation, and absence of an overall-survival benefit require cautious interpretation.
Aspirin has produced markedly different results depending on tumor type and molecular selection. In the Alliance A011502 phase III trial, 3,020 patients with high-risk, HER2-negative, non-metastatic breast cancer were randomized to receive 300 mg of aspirin daily or placebo. The study was terminated early after a median follow-up of 33.8 months. Aspirin did not improve survival free from invasive disease; there were 141 events in the aspirin group and 112 in the placebo group (HR 1.27; 95% CI 0.99–1.63; P=0.06). Overall survival also remained unchanged (HR 1.19; 95% CI 0.82-1.72). Grade ≥3 adverse events were comparable between the groups, suggesting that the poor outcome was due to a lack of efficacy rather than unacceptable toxicity. These findings do not support adjuvant aspirin in an unselected breast-cancer population [29]. By contrast, the ALASCCA trial provides strong evidence for biomarker-guided aspirin repurposing. This multinational, double-blind trial randomly assigned 626 patients with resected localized colorectal cancer, who had alterations in the PI3K-pathway, to receive either 160 mg/day of aspirin or a placebo for three years. Among patients with hotspot mutations in exon 9 or 20 of the PIK3CA gene, the three-year recurrence rate was 7.7% with aspirin compared with 14.1% with placebo (HR 0.49; 95% CI 0.24-0.98). A similar reduction was observed in patients with other clinically relevant alterations in the PIK3CA, PIK3R1 or PTEN genes (7.7% vs. 16.8%; HR 0.42; 95% CI 0.21-0.83). Disease-free survival also showed a more favourable trend with aspirin, particularly in the latest molecular cohort, although serious adverse events were more common with aspirin (16.8% vs. 11.6%) [30]. Taken together, these trials argue against indiscriminate aspirin use and support a precision-repurposing strategy where benefit is driven by biomarker selection.
Celecoxib followed a similar, but less conclusive, pattern. The CALGB/SWOG 80702 phase III trial evaluated whether celecoxib could improve outcomes when added to standard adjuvant FOLFOX (folinic acid, fluorouracil and oxaliplatin) in 2,526 patients with resected stage III colon cancer. Patients received 400 mg/day of celecoxib or a placebo for three years. After a median follow-up of six years, celecoxib did not meaningfully improve the primary endpoint: three-year disease-free survival was 76.3% with celecoxib and 73.4% with the placebo (HR 0.89; 95% CI 0.76-1.03; P=0.12). The five-year overall survival rate also showed no significant differences (84.3% vs. 81.6%; HR 0.86; 95% CI 0.72–1.04). Celecoxib was found to be associated with a higher rate of hypertension during treatment with FOLFOX and a higher incidence of grade ≥2 increases in creatinine following chemotherapy. Thus, the primary trial did not support unselected adjuvant celecoxib use [31]. Nevertheless, subsequent molecular analyses identified potentially responsive subgroups. Among 1,197 tumors with whole-exome sequencing, 259 carried activating PIK3CA mutations. In this cohort, celecoxib was associated with improved disease-free survival (adjusted HR 0.56; 95% CI 0.33-0.96) and better overall survival (adjusted HR 0.44; 95% CI 0.22-0.85), whilst only a limited benefit was observed in cancer with wild-type PIK3CA. The treatment-by-PIK3CA interaction was relevant for overall survival (P=0.04), but not for disease-free survival (P=0.13). The association appeared stronger in mismatch-repair-proficient cancers and after excluding baseline aspirin users, supporting, but not definitively validating, PIK3CA activation as a predictive biomarker for COX-2 inhibition [32]. A further post hoc analysis assessed postoperative circulating tumor DNA (ctDNA) in 940 patients. ctDNA was detected in 18.4% and was strongly prognostic: positivity was associated with approximately six-fold higher risks of disease recurrence or death and overall mortality. Among ctDNA-positive patients, celecoxib was linked to improved disease-free survival (adjusted HR 0.61; 95% CI 0.42-0.89) and overall survival (adjusted HR 0.62; 95% CI 0.40-0.96). No evidence of benefit was found in ctDNA-negative patients. However, formal interactions between treatment and ctDNA were not significant, and the study was retrospective and restricted to patients with available specimens [33]. Together, these studies show that celecoxib was ineffective as a broadly applied adjuvant treatment but may warrant prospective evaluation in patients with PIK3CA-activated tumors or postoperative molecular residual disease.
Two recent studies illustrate the limited translation of cardiovascular drugs into effective anticancer treatments when used without biomarker selection. The “PropAngio therapeutic window” study prospectively evaluated propranolol single therapy in 14 patients with angiosarcoma. Propranolol was administered in doses ranging from 80 to 240 mg per day for a period of 3-6 weeks prior to standard treatment. Only two patients met the predefined criteria for clinical benefit: one partial radiological response and one case of disease stabilisation with improvement in a skin lesion, corresponding to a response rate of 14%. One of five eligible patients also showed a partial metabolic response on FDG-PET. However, no histological response, defined as a >30% reduction in Ki-67, was observed. ADRB2 was upregulated in 16 of the 18 tumour samples but was present in both patients who responded to treatment and those who did not, indicating that receptor expression alone was not predictive of clinical benefit. Treatment was generally safe, although grade 1-2 bradycardia was frequent and prevented escalation to the maximum dose in most patients. Overall, the study did not meet its efficacy threshold and does not support propranolol monotherapy in unselected angiosarcoma, although occasional responses may justify further combination or biomarker-driven studies [34]. The AFPAC randomized trial compared the modified FOLFIRINOX treatment (folinic acid, fluorouracil, irinotecan and oxaliplatin) as monotherapy with the modified FOLFIRINOX treatment combined with losartan 50 mg/day in 88 previously untreated patients with locally advanced or metastatic pancreatic ductal adenocarcinoma. In this initial unplanned analysis, six-month overall survival was virtually identical between the two groups (72.7% vs. 73.2%), whilst median overall survival was 10.4 months with chemotherapy alone and 9.1 months with losartan. Median progression-free survival and tumor response rates also showed no significant improvement. Moreover, serial plasma TGF-β measurements showed no evidence that losartan modified the proposed stromal pathway. Toxicity and quality of life were comparable, although 22% of patients required temporary losartan interruption. Because no early efficacy signals emerged, the trial was terminated before full phase III patient recruitment. These findings suggest that renin–angiotensin-system blockade may not benefit advanced, predominantly metastatic pancreatic cancer, despite earlier encouraging results in localized disease [35]. Both examples support the use of functional measures for the tumor microenvironment rather than selection by receptor expression or disease site alone.
4.2. Autophagy Modulators and Anti-Infective Drugs
Hydroxychloroquine (HCQ) is being tested in oncology trials as a lysosomal and late-stage autophagy inhibitor, although clinically tolerable dosing has not consistently produced convincing intratumoral pathway inhibition. Clinical evidence for HCQ as an autophagy inhibitor remains context dependent. In a phase II randomized trial involving 59 patients with recurrent platinum-sensitive ovarian cancer, standard platinum-based chemotherapy was administered, either in combination with or without 200 mg of HCQ twice daily. Among 56 evaluable patients, HCQ did not significantly increase the objective response rate (85% vs. 80%; P=0.65). The median progression-free survival was 12 months with HCQ and 11 months with chemotherapy alone (HR 0.84; P=0.56), whilst the median overall survival was 16 and 21 months, respectively (P=0.49). HCQ did not produce a clear reduction in circulating autophagy-related biomarkers or improved quality of life. Toxicity was comparable between groups, indicating that the negative outcome primarily reflected lack of efficacy rather than poor tolerability. These results do not support the indiscriminate addition of HCQ at standard doses to platinum-based chemotherapy in recurrent ovarian cancer [36]. However, a single-arm phase Ib/II trial reported encouraging activity for HCQ in combination with a higher dose of palbociclib in 29 patients with advanced HR-positive/HER2-negative breast cancer, following failure of prior treatment with CDK4/6-inhibitors. HCQ 600 mg was administered twice daily without significantly altering palbociclib pharmacokinetics, and no dose-limiting toxicities occurred during dose increase. The recommended phase II regimen was HCQ plus palbociclib 200 mg/day. Among all participants, the objective response rate was 41.4%; in the dose-expansion cohort, the clinical benefit rate at six-month reached 90%, and median progression-free survival had not yet been achieved after approximately 32 weeks of follow-up. Grade 3 adverse events included neutropenia and leukopenia, each in 25% of expansion-cohort patients, together with fatigue and back pain. Paired tissue analyses showed reduced Ki-67 and phosphorylated AKT, increased p62, and greater LC3 accumulation in patients with better responses, supporting pharmacodynamic inhibition of autophagy. Nevertheless, the small sample, single-center, non-randomized design and limited follow-up prevent attribution of benefit specifically to HCQ and require confirmation in a controlled trial [37].
In a prospective, open-label, randomized study, 60 patients with metastatic non-small-cell lung cancer who had never previously received chemotherapy were treated with platinum-based chemotherapy and gemcitabine, with or without itraconazole at a dose of 200 mg/day during each treatment cycle. The addition of itraconazole increased the objective response rate from 66.7% to 90.0% (P=0.028) and the clinical benefit rate from 56.7% to 83.3% (P=0.024). Mean progression-free survival increased from approximately 5.4 to 6.4 months (P=0.002). Nevertheless, no difference in one-year overall survival was observed (approximately 9.5 vs. 9.7 months; P=0.702). Treatment was generally tolerable, although one patient developed a clinically relevant reduction in left-ventricular ejection fraction requiring itraconazole discontinuation. The small sample size, the open-label nature of the study, the short follow-up period and the use of chemotherapy treatments that are no longer the current first-line approach limit the generalizability of this encouraging finding [38]. Mixed results were obtained in the HYDRA-1 phase I trial, which evaluated the combination of itraconazole with HCQ to alter lysosomal homeostasis in platinum-resistant or refractory epithelial ovarian cancer. Preclinical screening across ovarian-cancer cell lines and genome-wide CRISPR analyses identified lysosomal and endosomal pathways as determinants of itraconazole sensitivity, and itraconazole plus HCQ showed synergistic cytotoxicity in vitro. Practically, 11 patients took 300 mg of itraconazole twice daily in combination with increasing doses of HCQ, thereby establishing a suggested dose for the phase II of 600 mg twice daily. The regimen was feasible and generally tolerable, but no objective responses were observed. Serial tumor biopsies demonstrated only limited pharmacodynamic effects, indicating that the strong preclinical lysosomal synergy was not reproduced adequately in patients [39]. Together, these studies suggest that itraconazole may provide modest chemotherapy-sensitizing activity in selected settings, but its clinical efficacy remains unconfirmed and appears highly dependent on tumor context, combination strategy, and demonstrable target engagement.
A window-of-opportunity study assessed whether atovaquone could reduce tumour hypoxia in patients with surgery-eligible non-small-cell lung cancer. Patients received 750 mg of atovaquone twice daily for a median duration of 12 days, or no treatment, prior to surgery. Of the 30 patients who could be assessed by PET–CT for hypoxia, 73.3% of those treated with atovaquone achieved a clinically significant reduction in hypoxic tumour volume, with a median change of -28.0%, versus a median increase of 15.5% in untreated patients. After adjustment for baseline hypoxia and tumor volume, hypoxic volume was estimated to be 55% lower in the atovaquone cohort (P=0.004). RNA-sequencing of resected tumours supported the imaging findings, showing significant downregulation of several hypoxia-related gene signatures, together with changes in oxidative-phosphorylation, glycolysis, reactive-oxygen-species, angiogenesis, and STAT3-associated pathways. Tumour perfusion and vascular density were not substantially altered, suggesting that improved oxygenation resulted mainly from reduced mitochondrial oxygen consumption rather than vascular normalization. Atovaquone was well tolerated and no treatment-related adverse events were reported. Although the study was small and non-randomized and did not assess clinical outcomes, it provides strong human proof of mechanism supporting atovaquone as a potential hypoxia-modifying radiosensitizer [40].
Two early-phase studies highlight how formulation and systemic exposure can determine the clinical feasibility of repurposed anthelmintic drugs. In a phase IIa study, personalized high-dose of mebendazole was administered to patients with treatment-refractory gastrointestinal cancers, using the therapeutic-drug monitoring to maintain a serum concentration of approximately 300 ng/mL. The trial was interrupted after 11 patients had been enrolled because adequate exposure was difficult to achieve and no clinical benefit was observed. Ten patients entered the treatment phase, and all discontinued because of radiological progression or clinical deterioration. Of the eight patients who were radiologically evaluable, none obtained an objective response; the median time to disease progression was just 59 days, compared with 162 days recorded with the previous treatment, and four patients met the proposed criteria for hyperprogressive disease. Although the doses reached 4 g/day and were generally well tolerated, only five patients in total achieved the target concentration, and only two managed to do so on more than one occasion. The study therefore suggests that the low bioavailability and high variability of mebendazole represent a significant obstacle to the development of conventional mebendazole-based formulations, such as systemic anticancer treatments [41]. By contrast, a reformulated niclosamide-based product, PDMX1001, achieved potentially active systemic concentrations in a phase Ib trial enrolling 9 men with metastatic castration-resistant prostate cancer. Niclosamide was combined with abiraterone and prednisone, and no dose-limiting toxicity occurred. The recommended dose for phase II was 1,200 mg three times a day; at this dose, the minimum and maximum concentrations measured exceeded the threshold for activity defined in the preclinical phase. Five out of eight evaluable patients achieved a ≥50% PSA reduction; two developed undetectable PSA levels accompanied by radiographic responses remaining on treatment for more than three years. The treatment regimen was usually well tolerated; the most common adverse event was diarrhea, whilst there were few cases of grade 3 toxicity. Nevertheless, efficacy cannot be attributed specifically to niclosamide because the study was small, non-randomized, and combined the repurposed agent with active standard therapy [42]. Together, these trials show that pharmacokinetic optimization is a prerequisite for clinical repurposing, but achieving adequate exposure does not exclude the need for controlled efficacy studies.
Clinical evaluation of repurposed antiretroviral drugs has produced predominantly negative or modest results. In the phase III NELCER trial, 92 patients with stage III cervical cancer were randomized to receive either modern radiotherapy or magnetic resonance-guided brachytherapy, with or without 1,250 mg of nelfinavir twice daily. At the planned interim analysis, three-year disease-free survival was 71% with standard treatment and 56% with nelfinavir (HR 1.34; 95% CI 0.66-2.70). Disease-specific survival also numerically favored the control arm (82% vs. 57%; HR 1.97), while acute grade ≥3 gastrointestinal toxicity was more frequent with nelfinavir (8.7% vs. 0%). As the regimen showed no efficacy and an unfavorable risk–benefit profile, recruitment was stopped early [43]. The multicenter SCALOP-2 trial also failed to demonstrate the efficacy of nelfinavir as a radiosensitizer in locally advanced pancreatic cancer. Following initial treatment with gemcitabine/nab-paclitaxel, patients were randomized to a chemoradiotherapy regimen based on standard- or high-dose capecitabine, with or without nelfinavir. Among the 76 patients randomized at the same time and included in the comparison with nelfinavir, median progression-free survival was 10.0 months with nelfinavir and 11.1 months without it (adjusted HR 1.71). Nelfinavir also failed to improve overall survival or other disease-control endpoints, although it did not substantially impair treatment compliance or increase grade 3–4 toxicity. Radiotherapy dose escalation modestly reduced local progression but did not improve overall survival [44]. In the single-arm, phase I PICCASSO trial, a different antiretroviral strategy was investigated, combining the CCR5 antagonist maraviroc with pembrolizumab in 20 patients with metastatic colorectal cancer who had mismatch repair function and microsatellite stability, and who had previously undergone intensive therapy. Treatment proved feasible in 94.7% of evaluable patients and was usually well tolerated, with only one grade 4 hyperglycemic event. However, clinical activity was limited: only one partial response was observed, the median progression-free survival was 2.1 months, and the median total survival was 9.83 months. Translational analyses suggested increased T-cell clustering and induction of proinflammatory chemokines, while higher eotaxin levels were associated with longer survival. Over 70% of evaluable patients reached disease control, leading to the discontinuation of emergency treatment, although this exploratory observation cannot establish a treatment-preparation effect [45]. Together, these studies show that pathway modulation and acceptable tolerability do not necessarily translate into meaningful clinical benefit. Nelfinavir should not be pursued as an unselected radiosensitizer in cervical or pancreatic cancer, whereas maraviroc-based immunomodulation remains biologically interesting but requires biomarker-guided and controlled evaluation. Further development of anti-infective drugs should start from a specific tumor or host dependency and include direct evidence that clinically achievable exposure modulates that dependency.
4.3. Neurological, Redox and Perioperative Strategies
Valproic acid (VPA) is an appealing candidate because it combines long clinical use, central-nervous-system penetration, and histone-deacetylase activity. However, clinical evidence for VPA in oncology remains preliminary and difficult to separate from the effects of concomitant treatments. In a phase II randomized trial, 88 patients with high-risk uveal melanoma, defined as monosomy of chromosome 3 with amplification of the 8q segment or a DecisionDx-UM class 2 profile for the assessment of metastatic risk, were treated for six months with 750 mg/day of VPA or 25 mg/day of sunitinib as adjuvant therapy. Both arms exceeded the prespecified historical benchmark of 70% for two-year overall survival, reaching 90.7% with VPA and 95.6% with sunitinib. However, 18-month relapse-free survival was lower with VPA than with sunitinib (62.8% vs. 75.6%), and multivariable analysis showed no significant difference between treatments. Any apparent advantage of sunitinib diminished after three years, while increasing primary-tumor diameter independently predicted progression. As the trial lacked untreated control and relied on historical survival estimates, it cannot establish that VPA reduced metastatic risk [46]. A phase I study with progressive dose escalation evaluated VPA in combination with bevacizumab and temsirolimus in 47 patients with advanced solid tumors who had undergone numerous previous treatments. The highest tolerated regimen comprised bevacizumab 5 mg/kg every two weeks, temsirolimus 25 mg one a week, and VPA 5 mg/kg on days 1-7 and 15-21 of each 28-day cycle. Among 38 patients evaluable for efficacy, the response rate was 7.9%, with partial responses observed in mucoepidermoid carcinoma of the parotid gland, endometrioid ovarian carcinoma and squamous cell carcinoma of the vagina. Five additional patients had stable diseases lasting at least six months, producing a clinical-benefit rate of 21%. The treatment was associated with significant toxicity: 95.7% of patients experienced treatment-related adverse events, and 55% reported grade 3-4 events, including lymphopenia, thrombocytopenia, mucositis, intestinal perforation and cerebrovascular ischemia [47]. Together, these studies provide limited evidence of VPA-associated activity. The absence of a placebo-controlled adjuvant comparison and the use of multidrug therapy prevent attribution of clinical benefit specifically to VPA. Future studies should relate unbound valproate concentrations to histone acetylation in tumor tissue while accounting for thrombocytopenia, hepatic toxicity, and interactions.
Randomized trials of pharmacological intravenous ascorbate administration have produced inconsistent results across tumor types. In a small open-label study of metastatic pancreatic ductal adenocarcinoma, 36 patients were randomized to receive gemcitabine/nab-paclitaxel, with or without intravenous ascorbate (75 mg three times a week); 34 received their assigned treatment. Ascorbate increased plasma concentrations of chemotherapeutics to the millimolar range and was associated with longer median overall survival (16.0 vs. 8.3 months; HR 0.46; 90% CI 0.23-0.92) and progression-free survival (6.2 vs. 3.9 months; HR 0.43; 90% CI 0.20-0.92). The objective response rates were 38% and 23% respectively. The addition of ascorbate did not impair quality of life or increase toxicity, and there were fewer cases of premature discontinuation of treatment due to adverse events occurred in the experimental group. However, the study was halted following an interim analysis, conducted using one-sided statistical test and 90% confidence intervals, with only 34 treated patients enrolled. Patients receiving ascorbate also remained on chemotherapy longer and received substantially higher cumulative chemotherapy doses, which complicate interpretation of the survival difference [48]. The phase III VITALITY trial provided a more definitive assessment in 442 previously untreated patients with unresectable metastatic colorectal cancer. The addition of high-dose vitamin C to the FOLFOX regimen, with or without bevacizumab, did not significantly improve median progression-free survival (8.6 vs. 8.3 months; HR 0.86; 95% CI 0.70-1.05), overall survival (20.7 vs. 19.7 months) or objective response rate (44.3% vs. 42.1%). Treatment-related adverse events of grade ≥3 were similar between the groups. A predetermined subgroup analysis indicated longer progression-free survival among patients with RAS-mutated tumors (9.2 vs. 7.8 months; HR 0.67; 95% CI 0.50-0.91), supporting a prospective evaluation based on biomarker selection rather than use in an unselected population of patients with colorectal-cancer [49]. By contrast, a double-blind, placebo-controlled phase II trial involving 47 men with castration-resistant metastatic prostate cancer showed no benefit from adding intravenous vitamin C to docetaxel. PSA50 response rates were 41% with ascorbate and 33% with placebo, while radiographic progression-free survival was virtually identical (10.1 vs. 10.0 months). Median overall survival was numerically shorter in the ascorbate-treated group (15.2 vs. 29.5 months), although the discrepancy was not statistically considerable. Toxicity, quality of life, and oxidative-stress biomarkers were also unchanged, and the trial was suspended for lack of benefit [50]. Taken together, these findings suggest that the use of ascorbate is not a widely effective anticancer treatment. The pancreatic cancer finding is encouraging but requires larger confirmatory trials, whereas studies in colorectal and prostate cancer emphasize the importance of tumor context and prospective biomarker selection.
Two trials investigating redox- and signaling-directed drug repurposing produced clearly negative clinical results. In a multicenter, randomized phase II/III trial, 88 patients with first-relapse glioblastoma were treated with standard alkylating chemotherapy as monotherapy or in combination with 400 mg/day of disulfiram and 2.5 mg/day of copper. The combination of disulfiram and copper did not enhance six-month survival, which was 44% in the experimental group compared with 62% with chemotherapy alone (P=0.10). Median overall survival was numerically shorter with the proposed combination (5.5 vs. 8.2 months), while median progression-free survival was similar (2.3 vs. 2.6 months). Toxicity was substantially greater: grade ≥3 adverse events occurred in 34% versus 11% of patients, serious adverse events in 41% versus 16%, and 24% discontinued disulfiram because of adverse effects. The trial was terminated early after an interim analysis revealed low conditional power with regard to benefits and an excess of serious toxicity [51]. A phase II proof-of-concept study evaluated auranofin at a dose of 6 mg/day in combination with sirolimus at a dose of 5 mg/day in patients with recurrent high-grade serous ovarian cancer, with the aim of inhibiting the protein kinase C iota (PKCι) signaling pathway. Twenty-two patients were recruited, and 21 were deemed evaluable. No objective responses were observed, triggering early termination according to the prespecified design. The median progression-free survival was 2.1 months (95% CI 1.8-3.7), whilst the median overall survival was 4.4 months (95% CI 2.6-12.5). Fourteen patients (67%) experienced at most one grade ≥3 adverse events. Tumor samples were available from 19 patients; all expressed PKCι, with a median PRKCI copy number of three per cell, yet this biomarker-defined population did not show clinical benefit [52]. Together, these studies illustrate that compelling preclinical mechanisms and tumor expression of the proposed target do not ensure clinical activity. Both combinations failed to improve outcomes and introduced substantial toxicity, challenging their further use in unselected patients without stronger pharmacodynamic evidence or a validated predictive biomarker.
Perioperative interventions produced contrasting results depending on whether the drug was delivered locally around the tumor or used as the general anesthetic. In a multicenter, randomized trial involving 1,583 women with operable breast cancer, peritumoral infiltration of 0.5% lidocaine 7-10 minutes before surgery was associated with improved disease-free survival and improved overall survival. After a median follow-up of 68 months, five-year disease-free survival was 86.6% with lidocaine compared with 82.6% without (HR 0.74; 95% CI 0.58-0.95), whilst five-year overall survival was 90.1% compared with 86.4% (HR 0.71; 95% CI 0.53-0.94). The benefit was consistent across all subgroups defined according to menopausal status, tumor size, nodal involvement, hormone receptor status and HER2 status. Distant recurrence was also reduced (8.5% vs. 11.6%; HR 0.73), and no adverse events were attributed to lidocaine. Although the trial was open label and requires external replication, it provides compelling evidence that a brief, low-cost intervention delivered directly around the tumor may influence metastatic recurrence [53]. On the contrary, randomized trials have not confirmed the hypothesis that intravenous anesthesia using propofol improves oncological outcomes compared with anesthesia using volatile anaesthetics. In a Chinese multicenter study, 1,195 patients aged between 65 and 90 years who underwent major, potentially curative oncological surgery were followed up for a median of 43 months. Overall survival was virtually identical between propofol and sevoflurane anesthesia: deaths occurred in 31% and 29% of patients, respectively (adjusted HR 1.02; 95% CI 0.83-1.26). Recurrence-free survival (adjusted HR 1.07) and event-free survival (adjusted HR 1.09) were likewise unaffected. These findings indicate that propofol should not be selected with the expectation of reducing recurrence or improving survival in older surgical oncology patients [54]. The larger-scale GA-CARES study confirmed this conclusion in a sample of 1,763 patients who had undergone resection of biologically aggressive tumors, including tumors of the pancreas, oesophagus, lung, stomach, hepatobiliary system, bladder and peritoneum. In the intention-to-treat analysis, mortality was 26.1% with propofol and 22.9% with volatile anesthetics (HR 1.16; 95% CI 0.96–1.41), with no improvement in disease-free survival (HR 1.10). In the prespecified per-protocol population, mortality was significantly higher with propofol (25.5% vs. 20.0%; HR 1.31), although this secondary analysis should not override the nonsignificant primary result [55]. Taken together, these studies suggest that the non-specific substitution of one general anesthetic for another does not improve the outcomes of cancer treatment, whilst the local administration of lidocaine, carried out at precisely defined times, may represent a more promising strategy for perioperative repurposing.
4.4. Multidrug Repurposing
Multidrug repurposing seeks to overcome tumor heterogeneity and treatment resistance by simultaneously modulating several biological pathways, but the available clinical evidence remains limited and mixed.
The CUSP9v3 phase Ib/IIa study evaluated nine repurposed non-oncology drugs, aprepitant, auranofin, captopril, celecoxib, disulfiram, itraconazole, minocycline, ritonavir, and sertraline, combined with continuous low dose temozolomide in ten adults with recurrent or progressive glioblastoma. All 9 patients evaluable for the primary endpoint were able to receive at least seven of the ten drugs at a dose equal to or greater than 50% of the planned dose without unmanageable grade 3-4 toxicity. Nausea, headache, fatigue, diarrhoea, and ataxia were common side effects, whilst ritonavir, temozolomide, captopril and itraconazole most frequently required treatment discontinuation or dose adjustment. Six patients achieved disease stabilisation; progression-free survival and overall survival at 12 months were both 50%, although the confidence intervals were wide. Five patients remained progression free for at least 12 months, including three with no detectable tumor on follow-up MRI. However, the trial was non-randomized, extremely small, and designed primarily to assess feasibility rather than efficacy [56]. The ModuLung randomized trial compared an oral biomodulatory regimen, comprising pioglitazone, clarithromycin, and low-dose treosulfan administered metronomically, with nivolumab in patients with previously treated advanced non-small-cell lung cancer. The trial was terminated early after immune checkpoint inhibitors were introduced as first-line treatment, leaving 37 patients available for analysis. Progression-free survival was markedly lower with biomodulation: 1.4 versus 1.6 months with nivolumab (HR 1.91; P=0.0483), whilst objective response rates were 5.0% and 11.8%, respectively. Median overall survival showed no significant difference (9.4 vs. 6.9 months), but 75% of patients in the biomodulation arm subsequently received checkpoint inhibitors, making it difficult to compare survival outcomes. Grade 3-5 treatment-related adverse events were less frequent with biomodulation than with nivolumab (10% vs. 29%). The proposed “priming” effect on subsequent immunotherapy remains speculative because it was not prospectively tested [57]. VESPA represents a more focused randomized multidrug strategy, although it has so far been reported as a study protocol, and clinical outcomes are not yet available. The study evaluates the efficacy of VPA and simvastatin as an adjunct to first-line gemcitabine/nab-paclitaxel chemotherapy in metastatic pancreatic ductal adenocarcinoma. The two repurposed drugs are intended to act on complementary mechanisms at the epigenetic level, within the mevalonate pathway, in tumor stem cells and in the epithelial-mesenchymal transition. VPA is titrated to a serum concentration of 50–100 μg/mL, while simvastatin is administered at 20 mg/day. The primary endpoint is progression-free survival, with an expected improvement of approximately six to nine months; translational studies include tumor profiling, circulating biomarkers, metabolomics, and pharmacokinetics. At the time of publication, recruitment was still ongoing and it was not possible to draw any conclusions about the efficacy [58]. Overall, these studies show that multidrug repurposing is clinically feasible under intensive monitoring, but regimen complexity increases interaction, toxicity, adherence, and component-attribution problems. Randomized evidence remains essential before biological breadth can be interpreted as therapeutic benefit.
5. Clinical Maturity: What Has Worked and What Has Not
The clinical evidence falls into four broad groups. The closest candidates to translation are those supported by positive randomized outcomes: aspirin in localized colorectal cancer with PI3K alterations, and peritumoral lidocaine in surgery for early-stage breast-cancer. Even these findings are context dependent. Aspirin must be considered alongside an individual patient's bleeding risk, and the lidocaine result still requires confirmation using the same route, concentration, and timing. A second group consists of promising results that are not sufficiently robust to support changes in clinical practice. This includes ascorbate in metastatic pancreatic cancer and simvastatin in recurrent small-cell lung cancer. A third group comprises hypotheses relating to biomarkers that have emerged from clinical trials which, on the whole, have yielded negative results: celecoxib in colon cancer with PIK3CA activation or ctDNA-positive tumors, metformin in high-volume metastatic prostate cancer, and ascorbate in colorectal cancer with a RAS gene mutation. These observations should be tested prospectively, with formal interaction analyses, rather than used to justify treatment outside a trial. Finally, the fourth group includes several other approaches that proved to be disappointing in the settings tested. Metformin repeatedly failed in unselected populations; nelfinavir did not improve chemoradiation outcomes; disulfiram-copper added toxicity without benefit; losartan was inactive in advanced pancreatic cancer; and propofol did not reduce postoperative recurrence. A further trial would be reasonable only if it changed something fundamental, such as the biomarker, formulation, route, achievable exposure, or clinical setting. This classification also helps separate proof of mechanism from proof of treatment benefit. Atovaquone reduced tumor hypoxia, and nelfinavir inhibited AKT in early studies, but neither observation is equivalent to a better clinical outcome. Registration of a trial, a change in a biomarker, or unusually long disease control in a small single-arm cohort should not be presented as evidence that a drug is an effective cancer treatment (Table 2).
6. Why Repurposed Drugs Fail
Repurposed drugs often share the same challenges that limit newly developed anticancer agents, with an additional risk: previous approval can create unjustified confidence in the dose and formulation. A recurrent problem is that experimental activity occurs at concentrations above clinically achievable unbound exposure. Metformin, mebendazole, niclosamide, hydroxychloroquine, and disulfiram highlight different aspects of the problem, including inadequate systemic concentration, poor absorption, uncertain active-metabolite formation, and limited tumor penetration.
The safety profile from the original indication may also be a poor guide to oncology use. Higher doses, longer treatment, organ dysfunction, and combination therapy can introduce bleeding, cardiovascular, renal, hepatic, retinal, neurological, or hematological toxicity. A drug that is familiar and inexpensive can still have an unfavorable incremental benefit-risk ratio when it is added to an effective standard treatment.
Biological heterogeneity is another major source of dilution. The contrast between aspirin in unselected breast cancer and in PI3K-altered colorectal cancer shows that tumor site alone is rarely enough. Simple target expression may also be misleading: beta-adrenergic-receptor expression did not predict response to propranolol, and expression of protein kinase C iota type did not identify ovarian tumors sensitive to auranofin.
Many early trials also lack direct evidence that the drug reaches and alters the intended target in human tumors. Peripheral blood markers may not reflect tumor pharmacology, and a negative efficacy study without intratumoral measurements cannot distinguish an incorrect mechanism from an inactive dose. Short presurgical studies, paired biopsies, functional imaging, therapeutic-drug monitoring, and measurement of active metabolites can resolve this uncertainty before a large efficacy trial is undertaken.
Development is further weakened by fragmentation. Small single-center studies, historical controls, changing standards of care, selective publication, and limited coordination can generate repeated preliminary signals without a definitive answer. For generic drugs, weak commercial incentives can delay or prevent confirmatory trials and formal regulatory development [10,59]. Negative and terminated studies should therefore be treated as useful evidence and reported with enough detail to prevent the same failure from being repeated.
7. Precision Repurposing, Regulation and Future Development
A more credible future for the field lies in precision repurposing: matching an established drug to a measurable tumor vulnerability, a clinically achievable exposure, and the clinical setting and treatment timing in which its pharmacology is most likely to matter. The relevant marker will not always be genomic. It may be pharmacodynamic, as with hypoxia imaging for atovaquone; metabolic or iron-related for pharmacological ascorbate; stromal for losartan; related to the immune-microenvironmental for propranolol; or dynamic, such as postoperative circulating tumor DNA. Biomarker analyses need to be planned and interpreted carefully. A ctDNA-positive population has a high baseline risk and may show a larger absolute benefit from any effective treatment without being specifically sensitive to the repurposed drug. Predictive claims therefore require a treatment-by-biomarker interaction, a reliable assay, and independent confirmation. Patient-derived functional assays can complement genomic data, but their drug concentrations must be clinically realistic, and tumor-cell assays cannot capture treatments that work mainly through immunity, platelets, stroma, or other host mechanisms [60].
A practical development sequence would start by confirming activity at achievable unbound concentrations, then moving to patient-derived models and an early-phase clinical pharmacology study. Only after exposure and target engagement have been demonstrated should a biomarker-enriched randomized phase II trial be considered. Adaptive platforms could share molecular screening, control groups, and translational assays while dropping inactive arms early. For multidrug regimens, pharmacokinetic monitoring and component-level evidence are needed to keep the combination interpretable. Regulatory planning cannot be postponed until after a positive trial. In Europe, the EMA/HMA repurposing initiative and subsequent scientific-advice support are intended to help academic and non-profit groups generate evidence suitable for authorization [59,61]. In the United States, a supplemental application or the 505(b)(2) route can make use of existing knowledge, but adequate evidence for the new indication is still required [62]. In either system, an applicant must take responsibility for product quality, labeling, pharmacovigilance, and supply. Nor is an inexpensive tablet necessarily an inexpensive treatment pathway. Biomarker testing, intravenous administration, imaging, therapeutic-drug monitoring, and management of interactions may account for much of the real cost. Public, charitable, and public-private funding should therefore support complete development programs rather than isolated exploratory trials. Where public investment establishes a new indication, access and affordability should be addressed from the outset.
8. Conclusions
Drug repurposing remains worth pursuing, but the evidence from 2021-2026 does not support the idea that an approved drug offers a simple shortcut to an effective cancer treatment. Most candidates evaluated in the trials reviewed here did not improve meaningful outcomes. Previous authorization tells us something about a drug's use in its original disease; it does not establish the dose, formulation, tumor exposure, or benefit-risk balance required in oncology. The clearest recent positive results were tightly linked to context: aspirin in PI3K-altered colorectal cancer and peritumoral lidocaine during breast cancer surgery. Ascorbate in pancreatic cancer and simvastatin in small-cell lung cancer warrant larger studies, whereas subgroup findings from negative trials should be used to design prospective research rather than to support off-label prescribing. Repurposed drugs should be developed with the same discipline applied to new anticancer agents. That means demonstrating achievable exposure and target engagement in the tumor or relevant host compartment, selecting patients prospectively, using a contemporary randomized comparator, reporting negative studies, and identifying an organization capable of carrying the program through regulation and implementation. The useful measure of progress is not how many old drugs enter trials, but how many complete this pathway and become reproducible, accessible treatments.
Author Contributions
Conceptualization, A.M. and M.V.R.; project administration, P.B. and V.S.; formal analysis, F.M.R.; data curation, M.B. and R.B.; visualization, S.G. and F.L.M.; investigation, M.B., R.B., S.G. and F.L.M.; methodology, F.M.R. and M.V.R.; supervision, P.B., A.M., M.V.R. and V.S.; validation, A.M. and M.V.R.; writing—original draft preparation, F.M.R. and M.V.R.; writing—review and editing, P.B., A.M., M.B., R.B., S.G., F.L.M. and V.S.. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analysed in this study. Data sharing is not applicable to this article.
Acknowledgments
During the preparation of this manuscript, the authors used ChatGPT (OpenAI) to support linguistic refinement, improve the organization and clarity of the text, and assist in the preparation of the graphical abstract. All AI-assisted content was critically reviewed and revised by the authors, who take full responsibility for the accuracy, originality, and integrity of the final manuscript.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ADRB2 | Adrenoceptor beta 2 |
| AKT | Protein kinase B |
| CCR5 | C–C chemokine receptor type 5 |
| CCL5 | C–C motif chemokine ligand 5 |
| CDK4/6 | Cyclin-dependent kinases 4 and 6 |
| CI | Confidence interval |
| COX-2 | Cyclooxygenase-2 |
| CRISPR | Clustered regularly interspaced short palindromic repeats |
| CTIS | Clinical Trials Information System |
| ctDNA | Circulating tumor DNA |
| CUSP9v3 | Coordinated Undermining of Survival Paths, version 3 |
| CYP3A4 | Cytochrome P450 3A4 |
| DFS | Disease-free survival |
| DNA | Deoxyribonucleic acid |
| EMA | European Medicines Agency |
| EudraCT | European Union Drug Regulating Authorities Clinical Trials Database |
| FDG-PET | Fluorodeoxyglucose positron-emission tomography |
| FOLFIRINOX | Folinic acid, Fluorouracil, Iirinotecan, and Oxaliplatin |
| FOLFOX | Folinic acid, Fluorouracil, and Oxaliplatin |
| GGPS1 | Geranylgeranyl diphosphate synthase 1 |
| GI | Gastrointestinal |
| HCQ | Hydroxychloroquine |
| HER2 | Human Epidermal Growth Factor Receptor 2 |
| HIV | Human Immunodeficiency Virus |
| HMA | Heads of Medicines Agencies |
| HR | Hazard Ratio |
| IDFS | Invasive Disease-Free Survival |
| LC3 | Microtubule-associated protein 1 light chain 3 |
| MEDLINE | Medical Literature Analysis and Retrieval System Online |
| MRI | Magnetic Resonance Imaging |
| MSS | Microsatellite stable |
| NSCLC | Non-Small-Cell Lung Cancer |
| OS | Overall Survival |
| PET–CT | Positron-Emission Tomography–Computed Tomography |
| PFS | Progression-Free Survival |
| PI3K | Phosphoinositide 3-kinase |
| PIK3CA | Phosphatidylinositol-4,5-bisphosphate 3-kinase catalytic subunit alpha |
| PIK3R1 | Phosphoinositide-3-kinase regulatory subunit 1 |
| PKCι | Protein kinase C iota |
| PSA | Prostate-Specific Antigen |
| PSA50 | Reduction in prostate-specific antigen of at least 50% from baseline |
| PTEN | Phosphatase and tensin homolog |
| RAS | Rat sarcoma family of small GTPases |
| ReDO | Repurposing Drugs in Oncology |
| RNA | Ribonucleic acid |
| SCLC | Small-Cell Lung Cancer |
| STAT3 | Signal transducer and activator of transcription 3 |
| TGF-β | Transforming Growth Factor beta |
| VPA | Valproic acid |
| WHO | World Health Organization |
References
- Sung, H.; Filho, A.M.; Laversanne, M.; Ferlay, J.; Siegel, R.L.; Soerjomataram, I.; Jemal, A.; Bray, F. Global Cancer Statistics 2024: GLOBOCAN Estimates of Incidence and Mortality Worldwide for 34 Cancers in 186 Countries. CA Cancer J. Clin. 2026, 76. [CrossRef]
- Spanò, V.; Barreca, M.; Rocca, R.; Bortolozzi, R.; Bai, R.; Carbone, A.; Raimondi, M.V.; Piccionello, A.P.; Montalbano, A.; Alcaro, S.; et al. Insight on [1,3]Thiazolo[4,5-e]Isoindoles as Tubulin Polymerization Inhibitors. Eur. J. Med. Chem. 2021, 212, 113122. [CrossRef]
- Barreca, M.; Spanò, V.; Raimondi, M. V.; Bivacqua, R.; Giuffrida, S.; Montalbano, A.; Cavalli, A.; Bertoni, F.; Barraja, P. GPCR Inhibition in Treating Lymphoma. ACS Med. Chem. Lett. 2022, 13, 358–364. [CrossRef]
- Barreca, M.; Ingarra, A.M.; Raimondi, M.V.; Spanò, V.; Piccionello, A.P.; De Franco, M.; Menilli, L.; Gandin, V.; Miolo, G.; Barraja, P.; et al. New Tricyclic Systems as Photosensitizers towards Triple Negative Breast Cancer Cells. Arch. Pharm. Res. 2022, 45, 806–821. [CrossRef]
- Labbozzetta, M.; Barreca, M.; Spanò, V.; Raimondi, M.V.; Poma, P.; Notarbartolo, M.; Barraja, P.; Montalbano, A. Novel Insights on [1,2]Oxazolo[5,4- e ]Isoindoles on Multidrug Resistant Acute Myeloid Leukemia Cell Line. Drug Dev. Res. 2022, 83, 1331–1341. [CrossRef]
- Cilibrasi, V.; Spanò, V.; Bortolozzi, R.; Barreca, M.; Raimondi, M.V.; Rocca, R.; Maruca, A.; Montalbano, A.; Alcaro, S.; Ronca, R.; et al. Synthesis of 2H-Imidazo[2′,1’:2,3] [1,3]Thiazolo[4,5-e]Isoindol-8-Yl-Phenylureas with Promising Therapeutic Features for the Treatment of Acute Myeloid Leukemia (AML) with FLT3/ITD Mutations. Eur. J. Med. Chem. 2022, 235, 114292. [CrossRef]
- Pushpakom, S.; Iorio, F.; Eyers, P.A.; Escott, K.J.; Hopper, S.; Wells, A.; Doig, A.; Guilliams, T.; Latimer, J.; McNamee, C.; et al. Drug Repurposing: Progress, Challenges and Recommendations. Nat. Rev. Drug Discov. 2019, 18, 41–58. [CrossRef]
- Pantziarka, P.; Verbaanderd, C.; Huys, I.; Bouche, G.; Meheus, L. Repurposing Drugs in Oncology: From Candidate Selection to Clinical Adoption. Semin. Cancer Biol. 2021, 68, 186–191. [CrossRef]
- Begley, C.G.; Ashton, M.; Baell, J.; Bettess, M.; Brown, M.P.; Carter, B.; Charman, W.N.; Davis, C.; Fisher, S.; Frazer, I.; et al. Drug Repurposing: Misconceptions, Challenges, and Opportunities for Academic Researchers. Sci. Transl. Med. 2021, 13. [CrossRef]
- Krishnamurthy, N.; Grimshaw, A.A.; Axson, S.A.; Choe, S.H.; Miller, J.E. Drug Repurposing: A Systematic Review on Root Causes, Barriers and Facilitators. BMC Health Serv. Res. 2022, 22, 970. [CrossRef]
- D’Amato, R.J.; Loughnan, M.S.; Flynn, E.; Folkman, J. Thalidomide Is an Inhibitor of Angiogenesis. Proceedings of the National Academy of Sciences 1994, 91, 4082–4085. [CrossRef]
- Vacca, A.; Scavelli, C.; Montefusco, V.; Di Pietro, G.; Neri, A.; Mattioli, M.; Bicciato, S.; Nico, B.; Ribatti, D.; Dammacco, F.; et al. Thalidomide Downregulates Angiogenic Genes in Bone Marrow Endothelial Cells of Patients With Active Multiple Myeloma. Journal of Clinical Oncology 2005, 23, 5334–5346. [CrossRef]
- Moreira, A.L.; Sampaio, E.P.; Zmuidzinas, A.; Frindt, P.; Smith, K.A.; Kaplan, G. Thalidomide Exerts Its Inhibitory Action on Tumor Necrosis Factor Alpha by Enhancing MRNA Degradation. J. Exp. Med. 1993, 177, 1675–1680. [CrossRef]
- Keifer, J.A.; Guttridge, D.C.; Ashburner, B.P.; Jr.Baldwin, A.S. Inhibition of NF-ΚB Activity by Thalidomide through Suppression of IκB Kinase Activity. Journal of Biological Chemistry 2001, 276, 22382–22387. [CrossRef]
- Geitz, H.; Handt, S.; Zwingenberger, K. Thalidomide Selectively Modulates the Density of Cell Surface Molecules Involved in the Adhesion Cascade. Immunopharmacology 1996, 31, 213–221. [CrossRef]
- Haslett, P.A.J.; Corral, L.G.; Albert, M.; Kaplan, G. Thalidomide Costimulates Primary Human T Lymphocytes, Preferentially Inducing Proliferation, Cytokine Production, and Cytotoxic Responses in the CD8+ Subset. J. Exp. Med. 1998, 187, 1885–1892. [CrossRef]
- Eleutherakis-Papaiakovou, V.; Bamias, A.; Dimopoulos, M.A. Thalidomide in Cancer Medicine. Annals of Oncology 2004, 15, 1151–1160.
- Singhal, S.; Mehta, J.; Desikan, R.; Ayers, D.; Roberson, P.; Eddlemon, P.; Munshi, N.; Anaissie, E.; Wilson, C.; Dhodapkar, M.; et al. Antitumor Activity of Thalidomide in Refractory Multiple Myeloma. New England Journal of Medicine 1999, 341, 1565–1571. [CrossRef]
- Barlogie, B.; Desikan, R.; Eddlemon, P.; Spencer, T.; Zeldis, J.; Munshi, N.; Badros, A.; Zangari, M.; Anaissie, E.; Epstein, J.; et al. Extended Survival in Advanced and Refractory Multiple Myeloma after Single-Agent Thalidomide: Identification of Prognostic Factors in a Phase 2 Study of 169 Patients. Blood 2001, 98, 492–494. [CrossRef]
- Dimopoulos, M.A.; Zervas, K.; Kouvatseas, G.; Galani, E.; Grigoraki, V.; Kiamouris, Ch.; Vervessou, E.; Samantas, E.; Papadimitriou, Ch.; Economou, O.; et al. Thalidomide and Dexamethasone Combination for Refractory Multiple Myeloma. Annals of Oncology 2001, 12, 991–995. [CrossRef]
- Kropff, M.H.; Lang, N.; Bisping, G.; Dominé, N.; Innig, G.; Hentrich, M.; Mitterer, M.; Südhoff, T.; Fenk, R.; Straka, C.; et al. Hyperfractionated Cyclophosphamide in Combination with Pulsed Dexamethasone and Thalidomide (HyperCDT) in Primary Refractory or Relapsed Multiple Myeloma. Br. J. Haematol. 2003, 122, 607–616. [CrossRef]
- clinicaltrials.eu Thalidomide Available online: https://clinicaltrials.eu/drug/thalidomide/ (accessed on 5 August 2026).
- Pantziarka, P.; Vandeborne, L.; Bouche, G. A Database of Drug Repurposing Clinical Trials in Oncology. Front. Pharmacol. 2021, 12. [CrossRef]
- Goodwin, P.J.; Chen, B.E.; Gelmon, K.A.; Whelan, T.J.; Ennis, M.; Lemieux, J.; Ligibel, J.A.; Hershman, D.L.; Mayer, I.A.; Hobday, T.J.; et al. Effect of Metformin vs Placebo on Invasive Disease–Free Survival in Patients With Breast Cancer. JAMA 2022, 327, 1963. [CrossRef]
- Romero, I.L.; Lengyel, E.; Wahner Hendrickson, A.E.; Rodriguez, G.C.; Leath, C.A.; Rocconi, R.P.; Goodheart, M.J.; Dewdney, S.; Karrison, T.; Fleming, G.F.; et al. Metformin for Patients with Advanced Stage Ovarian Cancer: A Randomized Phase II Placebo-Controlled Trial. Gynecol. Oncol. 2025, 194, 18–24. [CrossRef]
- Fleshner, N.E.; Bernardino, R.M.; Izawa, J.; Drachenberg, D.; Saranchuk, J.W.; Fairey, A.; Tanguay, S.; Leveridge, M.; Saad, F.; Breau, R.H.; et al. Metformin Active Surveillance Trial in Low-Risk Prostate Cancer. Journal of Clinical Oncology 2025, 43, 3662–3671. [CrossRef]
- Gillessen, S.; Murphy, L.; James, N.D.; Sachdeva, A.; El-Taji, O.; Abdel-Aty, H.; Adler, A.I.; Amos, C.; Attard, G.; Varughese, M.; et al. Metformin for Patients with Metastatic Prostate Cancer Starting Androgen Deprivation Therapy: A Randomised Phase 3 Trial of the STAMPEDE Platform Protocol. Lancet Oncol. 2025, 26, 1018–1030. [CrossRef]
- Guan, M.; Zhao, W.; Zhang, W.; Chen, X.; Huang, R.; Liu, X.; Li, Y.; Wang, H.; Zhao, L.; Xu, K.; et al. Efficacy and Safety of Albumin-Bound Paclitaxel Combined with Simvastatin in the Second-Line Treatment of Small Cell Lung Cancer: A Phase II Randomized Controlled Trial. BMC Med. 2026, 24, 383. [CrossRef]
- Chen, W.Y.; Ballman, K. V.; Partridge, A.H.; Hahn, O.M.; Briccetti, F.M.; Irvin, W.J.; Symington, B.; Visvanathan, K.; Pohlmann, P.R.; Openshaw, T.H.; et al. Aspirin vs Placebo as Adjuvant Therapy for Breast Cancer. JAMA 2024, 331, 1714. [CrossRef]
- Martling, A.; Hed Myrberg, I.; Nilbert, M.; Grönberg, H.; Granath, F.; Eklund, M.; Öresland, T.; Iversen, L.H.; Haapamäki, C.; Janson, M.; et al. Low-Dose Aspirin for PI3K-Altered Localized Colorectal Cancer. New England Journal of Medicine 2025, 393, 1051–1064. [CrossRef]
- Meyerhardt, J.A.; Shi, Q.; Fuchs, C.S.; Meyer, J.; Niedzwiecki, D.; Zemla, T.; Kumthekar, P.; Guthrie, K.A.; Couture, F.; Kuebler, P.; et al. Effect of Celecoxib vs Placebo Added to Standard Adjuvant Therapy on Disease-Free Survival Among Patients With Stage III Colon Cancer. JAMA 2021, 325, 1277. [CrossRef]
- Nowak, J.A.; Twombly, T.; Ma, C.; Shi, Q.; Haruki, K.; Fujiyoshi, K.; Väyrynen, J.; Zhao, M.; Knight, J.; Mane, S.; et al. Improved Survival With Adjuvant Cyclooxygenase 2 Inhibition in PIK3CA -Activated Stage III Colon Cancer: CALGB/SWOG 80702 (Alliance). Journal of Clinical Oncology 2024, 42, 2853–2859. [CrossRef]
- Zhang, G.Q.; Meyerhardt, J.A.; Shi, Q.; Twombly, T.; Pederson, L.; Ma, C.; Väyrynen, J.P.; Zhao, M.; Takashima, Y.; Shergill, A.; et al. Predictive Role of Circulating Tumor DNA in Stage III Colon Cancer Treated With Celecoxib. JAMA Oncol. 2026, 12, 149. [CrossRef]
- Embaby, A.; Heinhuis, K.M.; IJzerman, N.S.; Koenen, A.M.; van der Kleij, S.; Hofland, I.; van Boven, H.; Sanders, J.; van der Graaf, W.T.A.; Haas, R.L.; et al. Propranolol Monotherapy in Angiosarcoma – A Window-of-Opportunity Study (PropAngio). Eur. J. Cancer 2024, 202, 113974. [CrossRef]
- Ramaswamy, A.; Bhargava, P.; Gota, V.; Srinivas, S.; Sultana, N.; Mandavkar, S.; Jadhav, P.; Gandhi, K.; Mer, N.; Khan, N.; et al. Efficacy of Losartan plus Modified FOLFIRINOX versus Modified FOLFIRINOX in Advanced Pancreatic Cancers: A Randomized Clinical Trial (AFPAC Study). Cancer 2025, 131. [CrossRef]
- Goenka, L.; Dubashi, B.; Kayal, S.; Rajappa, M.; Manivannan, P.; Chakkalakkoombil, S.V.; Gochhait, D.; Chaturvedula, L.; Pradeep, S.; Anandaradje, A.; et al. Targeting Autophagy in Platinum-Sensitive Relapsed Ovarian Cancer: Randomized Phase II Trial of Hydroxychloroquine with Chemotherapy with Biomarker Correlation. Discover Oncology 2025, 16, 203. [CrossRef]
- Gong, C.; Lin, Q.; Qin, T.; Zeng, Y.; Xu, F.; Yang, Y.; Yin, D.; Duan, Z.; Chen, C.-L.; Wing-Cheong Chow, L.; et al. Targeting Autophagy plus High-Dose CDK4/6 Inhibitors in Advanced HR+HER2− Breast Cancer: A Phase 1b/2 Trial. Med 2025, 6, 100559. [CrossRef]
- Mohamed, A.W.; Elbassiouny, M.; Elkhodary, D.A.; Shawki, M.A.; Saad, A.S. The Effect of Itraconazole on the Clinical Outcomes of Patients with Advanced Non-Small Cell Lung Cancer Receiving Platinum-Based Chemotherapy: A Randomized Controlled Study. Medical Oncology 2021, 38, 23. [CrossRef]
- Marastoni, S.; Madariaga, A.; Pesic, A.; Nair, S.N.; Li, Z.J.; Shalev, Z.; Ketela, T.; Colombo, I.; Mandilaras, V.; Cabanero, M.; et al. Repurposing Itraconazole and Hydroxychloroquine to Target Lysosomal Homeostasis in Epithelial Ovarian Cancer. Cancer Research Communications 2022, 2, 293–306. [CrossRef]
- Skwarski, M.; McGowan, D.R.; Belcher, E.; Di Chiara, F.; Stavroulias, D.; McCole, M.; Derham, J.L.; Chu, K.-Y.; Teoh, E.; Chauhan, J.; et al. Mitochondrial Inhibitor Atovaquone Increases Tumor Oxygenation and Inhibits Hypoxic Gene Expression in Patients with Non–Small Cell Lung Cancer. Clinical Cancer Research 2021, 27, 2459–2469. [CrossRef]
- Mansoori, S.; Fryknäs, M.; Alvfors, C.; Loskog, A.; Larsson, R.; Nygren, P. A Phase 2a Clinical Study on the Safety and Efficacy of Individualized Dosed Mebendazole in Patients with Advanced Gastrointestinal Cancer. Sci. Rep. 2021, 11, 8981. [CrossRef]
- Parikh, M.; Liu, C.; Wu, C.-Y.; Evans, C.P.; Dall’Era, M.; Robles, D.; Lara, P.N.; Agarwal, N.; Gao, A.C.; Pan, C.-X. Phase Ib Trial of Reformulated Niclosamide with Abiraterone/Prednisone in Men with Castration-Resistant Prostate Cancer. Sci. Rep. 2021, 11, 6377. [CrossRef]
- Chopra, S.; Mittal, P.; Gupta, A.; Goda, J.S.; Pai, V.; Kannan, S.; Menon, S.; Deodhar, K.; Jain, J.; Sawant, P.; et al. Chemoradiation and Image-Guided Brachytherapy Alone or in Combination With Protease Inhibitor (Nelfinavir Mesylate) in Stage III Cervical Cancer: Results From a Phase III Trial. JCO Oncology Advances 2026, 3. [CrossRef]
- Mukherjee, S.; Qi, C.; Shaw, R.; Jones, C.M.; Bridgewater, J.A.; Radhakrishna, G.; Patel, N.; Holmes, J.; Virdee, P.S.; Tranter, B.; et al. Standard or High Dose Chemoradiotherapy, with or without the Protease Inhibitor Nelfinavir, in Patients with Locally Advanced Pancreatic Cancer: The Phase 1/Randomised Phase 2 SCALOP-2 Trial. Eur. J. Cancer 2024, 209, 114236. [CrossRef]
- Haag, G.M.; Springfeld, C.; Grün, B.; Apostolidis, L.; Zschäbitz, S.; Dietrich, M.; Berger, A.-K.; Weber, T.F.; Zoernig, I.; Schaaf, M.; et al. Pembrolizumab and Maraviroc in Refractory Mismatch Repair Proficient/Microsatellite-Stable Metastatic Colorectal Cancer – The PICCASSO Phase I Trial. Eur. J. Cancer 2022, 167, 112–122. [CrossRef]
- Seedor, R.S.; Orloff, M.M.; Sharpe-Mills, E.; Hulse, L.; Shelat, R.; Shimada, A.; Chervoneva, I.; Shields, C.L.; Shields, J.A.; Mastrangelo, M.J.; et al. Randomized Phase II Study of Adjuvant Sunitinib or Valproic Acid in High-Risk Patients with Uveal Melanoma: The Final Analysis of Cohort 1. Journal of Clinical Oncology 2022, 40, 9586–9586. [CrossRef]
- Nelson, B.E.; Tsimberidou, A.M.; Fu, X.; Fu, S.; Subbiah, V.; Sood, A.K.; Rodon, J.; Karp, D.D.; Blumenschein, G.; Kopetz, S.; et al. A Phase I Trial of Bevacizumab and Temsirolimus in Combination With Valproic Acid in Advanced Solid Tumors. Oncologist 2023, 28, 1100-e1292. [CrossRef]
- Bodeker, K.L.; Smith, B.J.; Berg, D.J.; Chandrasekharan, C.; Sharif, S.; Fei, N.; Vollstedt, S.; Brown, H.; Chandler, M.; Lorack, A.; et al. A Randomized Trial of Pharmacological Ascorbate, Gemcitabine, and Nab-Paclitaxel for Metastatic Pancreatic Cancer. Redox Biol. 2024, 77, 103375. [CrossRef]
- Wang, F.; He, M.-M.; Xiao, J.; Zhang, Y.-Q.; Yuan, X.-L.; Fang, W.-J.; Zhang, Y.; Wang, W.; Hu, X.-H.; Ma, Z.-G.; et al. A Randomized, Open-Label, Multicenter, Phase 3 Study of High-Dose Vitamin C Plus FOLFOX ± Bevacizumab versus FOLFOX ± Bevacizumab in Unresectable Untreated Metastatic Colorectal Cancer (VITALITY Study). Clinical Cancer Research 2022, 28, 4232–4239. [CrossRef]
- Paller, C.J.; Zahurak, M.L.; Mandl, A.; Metri, N.A.; Lalji, A.; Heath, E.; Kelly, W.K.; Hoimes, C.; Barata, P.; Taksey, J.; et al. High-Dose Intravenous Vitamin C Combined with Docetaxel in Men with Metastatic Castration-Resistant Prostate Cancer: A Randomized Placebo-Controlled Phase II Trial. Cancer Research Communications 2024, 4, 2174–2182. [CrossRef]
- Werlenius, K.; Kinhult, S.; Solheim, T.S.; Magelssen, H.; Löfgren, D.; Mudaisi, M.; Hylin, S.; Bartek, J.; Strandéus, M.; Lindskog, M.; et al. Effect of Disulfiram and Copper Plus Chemotherapy vs Chemotherapy Alone on Survival in Patients With Recurrent Glioblastoma. JAMA Netw. Open 2023, 6, e234149. [CrossRef]
- Jatoi, A.; Foster, N.R.; Wahner Hendrickson, A.; Block, M.S.; Weroha, S.J.; Asmus, E.J.; Murray, N.R.; Fields, A.P. A Phase 2 Trial of Protein Kinase C Iota Inhibition With the Combination of Auranofin and Sirolimus in Patients With Recurrent Ovarian Cancer. Am. J. Clin. Oncol. 2026, 49, 238–242. [CrossRef]
- Badwe, R.A.; Parmar, V.; Nair, N.; Joshi, S.; Hawaldar, R.; Pawar, S.; Kadayaprath, G.; Borthakur, B.B.; Rao Thammineedi, S.; Pandya, S.; et al. Effect of Peritumoral Infiltration of Local Anesthetic Before Surgery on Survival in Early Breast Cancer. Journal of Clinical Oncology 2023, 41, 3318–3328. [CrossRef]
- Cao, S.-J.; Zhang, Y.; Zhang, Y.-X.; Zhao, W.; Pan, L.-H.; Sun, X.-D.; Jia, Z.; Ouyang, W.; Ye, Q.-S.; Zhang, F.-X.; et al. Long-Term Survival in Older Patients given Propofol or Sevoflurane Anaesthesia for Major Cancer Surgery: Follow-up of a Multicentre Randomised Trial. Br. J. Anaesth. 2023, 131, 266–275. [CrossRef]
- Bennett-Guerrero, E.; Romeiser, J.L.; DeMaria, S.; Nadler, J.W.; Quinn, T.D.; Ponnappan, S.K.; Wang, R.; Gloff, M.S.; Lee, K.J.; Levin, M.A.; et al. Anesthesia Type during Cancer Surgery: Results of the GA-CARES Randomized, Multicenter Trial. Anesthesiology 2026, 144, 51–62. [CrossRef]
- Halatsch, M.-E.; Kast, R.E.; Karpel-Massler, G.; Mayer, B.; Zolk, O.; Schmitz, B.; Scheuerle, A.; Maier, L.; Bullinger, L.; Mayer-Steinacker, R.; et al. A Phase Ib/IIa Trial of 9 Repurposed Drugs Combined with Temozolomide for the Treatment of Recurrent Glioblastoma: CUSP9v3. Neurooncol. Adv. 2021, 3. [CrossRef]
- Heudobler, D.; Schulz, C.; Fischer, J.R.; Staib, P.; Wehler, T.; Südhoff, T.; Schichtl, T.; Wilke, J.; Hahn, J.; Lüke, F.; et al. A Randomized Phase II Trial Comparing the Efficacy and Safety of Pioglitazone, Clarithromycin and Metronomic Low-Dose Chemotherapy with Single-Agent Nivolumab Therapy in Patients with Advanced Non-Small Cell Lung Cancer Treated in Second or Further Line (ModuLung). Front. Pharmacol. 2021, 12. [CrossRef]
- Budillon, A.; Leone, A.; Passaro, E.; Silvestro, L.; Foschini, F.; Iannelli, F.; Roca, M.S.; Macchini, M.; Bruzzese, F.; Garcia Bermejo, M.L.; et al. Randomized Phase 2 Study of Valproic Acid Combined with Simvastatin and Gemcitabine/Nab-Paclitaxel-Based Regimens in Untreated Metastatic Pancreatic Adenocarcinoma Patients: The VESPA Trial Study Protocol. BMC Cancer 2024, 24, 1167. [CrossRef]
- Asker-Hagelberg, C.; Boran, T.; Bouygues, C.; Eskola, S.M.; Helmle, L.; Hernández, C.; Houýez, F.; Lee, H.; Lingri, D.D.; Louette, L.; et al. Repurposing of Medicines in the EU: Launch of a Pilot Framework. Front. Med. (Lausanne). 2022, 8. [CrossRef]
- van Renterghem, A.W.J.; van de Haar, J.; Voest, E.E. Functional Precision Oncology Using Patient-Derived Assays: Bridging Genotype and Phenotype. Nat. Rev. Clin. Oncol. 2023, 20, 305–317.
- European Medicines Agency EU Repurposing Pilot Report by the EU Regulatory Network on the Learnings and Recommendations from Testing a Proposal for a Framework to Support Not-for-Profit Organisations and Academia in Drug Repurposing; 2025;
- U. S. Department of Health and Human Services Food and Drug Administration Center for Drug Evaluation and Research (CDER) Guidance for Industry Applications Covered by Section 505(b)(2); 1999;

Table 1.
Clinically informative repurposing trials, 1 January 2021-31 July 2026.
| Drug | Original use | Cancer type/ study | Trial design | Main finding | Clinical interpretation |
|---|---|---|---|---|---|
| Metformin | Type 2 diabetes | High-risk breast cancer, MA.32 | NCT01101438 [1] Phase III; n=3649* |
No IDFS or OS benefit | Not supported as routine adjuvant therapy in non-diabetic patients |
| Metformin | Type 2 diabetes | Ovarian and prostate cancer | NCT02122185 [2] NCT01864096 [3] NCT00268476 [4] Randomized phase II/III |
No overall benefit; high-volume prostate subgroup exploratory | Further metabolic or molecular selection is required |
| Simvastatin | Hypercholesterolemia | Relapsed SCLC | NCT04698941 [5] Randomized phase II; n=40* |
Response and PFS improved; OS did not | Encouraging, but small and single-center |
| Aspirin | Antiplatelet; analgesic | High-risk HER2-negative breast cancer, Alliance A011502 | NCT02927249 [6] Phase III; n=3020* |
Stopped for futility; no IDFS or OS benefit | No established role in an unselected population |
| Aspirin | Antiplatelet; analgesic | PI3K-altered localized colorectal cancer, ALASCCA | NCT02647099 [7] Randomized, placebo-controlled; n=626* |
Recurrence reduced in both molecular cohorts | Strong biomarker-directed signal; bleeding risk remains |
| Celecoxib | COX-2 inhibitor | Stage III colon cancer, CALGB/SWOG 80702 | NCT01150045 [8,9,10] Phase III; n=2526* |
Overall trial negative; subgroup signals in PIK3CA-activated and ctDNA-positive disease | Prospective biomarker-selected validation is needed |
| Propranolol | Beta-blocker | Angiosarcoma, PropAngio | NCT04518124 [11] Window study; n=14* |
Limited activity despite frequent ADRB2 expression | ADRB2 expression alone was not predictive |
| Losartan | Hypertension | Advanced pancreatic cancer, AFPAC | CTRI/2021/05/033482 [12] Randomized; n=88* |
No response or survival benefit | Stromal selection and perfusion measures may be required |
| Hydroxychloroquine | Antimalarial; autoimmune disease | Recurrent ovarian cancer | CTRI/2020/06/025790 [13] Randomized phase II; n=59* |
No response, PFS, or OS benefit; target engagement uncertain | Tumor pharmacodynamics should precede further trials |
| Hydroxychloroquine | Antimalarial; autoimmune disease | HR-positive/HER2-negative breast cancer | NCT05953350 [14] Small phase I/Ib-II combinations |
Responses occurred in palbociclib-based regimens | The HCQ contribution cannot be isolated |
| Itraconazole | Antifungal | Metastatic NSCLC; refractory ovarian cancer, HYDRA |
NCT03664115 [15] NCT03081702 [16] Small randomized study; phase I |
NSCLC PFS signal without OS benefit; no HYDRA responses | Exposure and CYP3A4 interactions complicate interpretation |
| Atovaquone | Antiprotozoal | Resectable NSCLC, ATOM | NCT02628080 [17] Window study; n=30* |
Tumor hypoxia and hypoxic gene expression decreased | Proof of mechanism, not yet proof of benefit |
| Mebendazole / niclosamide | Anthelmintics | Advanced GI cancer; castration-resistant prostate cancer PDMX1001 |
NCT03628079 [18] NCT02807805 [19] Phase IIa; phase Ib |
Mebendazole exposure was inadequate; reformulated niclosamide reached target levels | Systemic bioavailability depends on formulation |
| Nelfinavir | HIV protease inhibitor | Cervical cancer, NELCER; pancreatic cancer, SCALOP-2 | NCT03256916 [20] NCT02024009 [21] Randomized phase III / II |
No clinical benefit; GI toxicity increased in NELCER | AKT modulation did not translate into radiosensitization |
| Maraviroc | CCR5 antagonist | MSS metastatic colorectal cancer, PICCASSO | NCT03274804 [22] Phase I with pembrolizumab |
Feasible and immunomodulatory; activity was limited | Selection for active CCR5-CCL5 signaling is needed |
| Valproic acid | Antiepileptic; mood stabilizer | High-risk uveal melanoma; advanced solid tumors | NCT02068586 [23] NCT01552434 [24] Randomized phase II cohort; phase I combination |
No comparative benefit; combination activity was modest | A valproate-specific effect remains unproven |
| Pharmacological ascorbate | Vitamin replacement | Metastatic colorectal, pancreatic, and prostate cancer; VITALITY | NCT02905578 [25] NCT02969681 [26] NCT02516670 [27] Phase III and randomized phase II |
Colorectal and prostate trials negative; pancreatic signal positive | Pancreatic findings require multicenter confirmation |
| Disulfiram-copper / auranofin | Alcohol dependence / rheumatoid arthritis | Glioblastoma; recurrent ovarian cancer | NCT02678975 [28] NCT03456700 [29] Randomized trial; phase II |
Disulfiram increased toxicity without benefit; no auranofin-sirolimus responses | Systemic exposure did not ensure intratumoral activity |
| Lidocaine | Local anesthetic | Early breast-cancer surgery; GA-CARES | NCT01916317 [30] Randomized; n=1583* |
Peritumoral injection associated with longer 5-year DFS and OS | Important perioperative signal; replication is needed |
| Propofol | Intravenous anesthetic | Major cancer surgery | NCT02660411 [31] NCT03034096 [32] Randomized long-term analyses |
No OS or DFS advantage | Anesthetic choice should not rely on an anticancer claim |
| Multiple Repurposed agents | Combination therapy | Glioblastoma; NSCLC; pancreatic cancer CUSP9v3 / ModuLung / VESPA | NCT02770378 [33] NCT02852083 [34] NCT05821556 [35] Feasibility; randomized phase II; ongoing phase II |
CUSP9v3 feasible but uncontrolled; ModuLung inferior PFS; VESPA ongoing | Complexity complicates adherence, interactions, and attribution |
* Number of enrolled patients.
Table 2.
Provisional clinical-maturity framework.
| Level | Examples | Implication |
|---|---|---|
| Positive randomized evidence | Aspirin in PI3K-altered colorectal cancer; peritumoral lidocaine in early breast-cancer surgery | Could be clinically relevant but limited to the population and intervention actually tested. Guideline assessment and replication are still needed |
| Promising but unconfirmed | Pharmacological ascorbate in pancreatic cancer; simvastatin in relapsed small-cell lung cancer | Larger multicenter randomized studies should confirm the signal and include prospective pharmacodynamic markers |
| Biomarker hypothesis from a negative overall trial | Celecoxib in PIK3CA-activated or ctDNA-positive colon cancer; metformin in high-volume prostate cancer; ascorbate in RAS-mutated colorectal cancer | Research hypotheses, not yet treatment indications, that require prospectively enriched trials |
| Negative or insufficiently supported | Metformin in unselected cancers; nelfinavir; disulfiram-copper; losartan in advanced pancreatic cancer; propofol; mebendazole; auranofin | Further investigation is warranted only if it addresses the prior failure, such as exposure, formulation, biomarker, or clinical setting |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.