

Submitted:
28 September 2026
Posted:
30 September 2026
You are already at the latest version
Abstract
Background: Mobile technologies are increasingly viewed as tools for connecting African populations with healthcare systems, yet whether phone ownership, internet access, and frequency of use are independently related to healthcare contact, after accounting for socioeconomic, demographic, and regional differences, remains unclear. Methods: We analysed pooled cross-sectional data of 44,761 respondents in Round 8 of the Afrobarometer survey across five regions in Africa. The outcome variable was self-reported contact with a public clinic or hospital in the previous 12months. Primary exposures were phone ownership, phone-based internet access, and frequency of phone use. Sequential multivariable logistic regression models assessed their independent relationships before and after adjustment for age, sex, education, religion, rural residence, and African region. A separate model examined whether lived poverty modified the relationship between internet access and healthcare contact using poverty-by-internet-access interaction terms. Results: Overall, 61.1% of respondents reported contact with a public clinic or hospital in the last 12months. Phone ownership was not independently related to contact after full adjustment (AOR=1.054, 95% CI 0.950-1.170; p=.268). Internet access was positively linked with contact after full adjustment (AOR=1.081, 95% CI 1.033-1.131; p< 0.001), despite an inverse relationship before adjustment (AOR=0.850, 95% CI 0.818-0.883). Frequency of use showed the most consistent relationship, with daily users having higher odds of contact than never-users (AOR=1.217, 95% CI 1.091-1.357). Lived poverty was independently related to contact with healthcare facility, with the highest odds among those reporting moderate poverty (AOR=1.709, 95% CI 1.528-1.911), but did not modify the internet access-contact relationship (all interaction p≥.553). Regional disparities were substantial, with lower odds of contact found in Northern Africa than in West Africa (AOR=0.411-0.437 across models). Conclusion: Mobile-phone engagement dimensions showed distinct links with healthcare contact. Frequency of use was most consistently related, while internet access showed a positive connection after covariate and factor adjustment; phone ownership alone was not independently related. The absence of effect modification by lived poverty suggests no detectable heterogeneity in the internet access-contact link across poverty levels. Persistent regional disparities highlight the importance of contextual determinants beyond mobile access.
Keywords:
mobile phone use
; internet access
; mobile phone ownership
; lived poverty
; effect modification
; healthcare access
; Africa
Introduction
Geographic, technical and socio-economic barriers continue to shape/constrain equitable access to healthcare in Africa. Socio-economic barriers have been widely studied in low and middle-income countries (LMICs), for example, financial hardship is often identified as one of the topmost barriers to healthcare access, while distance, transport costs, and health-system constraints such as patient waiting time and scarcity of medical supplies further influence healthcare utilisation (Dawkins et al., 2021). Geographic distribution of population vis-à-vis healthcare services also mediate access. These barriers tend to operate in interactive manner, resulting in the moderation or amplification of the effect of one another. With increasing digitization and digitalization of healthcare services, it is important to understand how access to digital services through mobile phones and internet mediate access to healthcare services in developing countries. Understanding whether expanding digital connectivity can contribute to healthcare engagement therefore requires attention to both technological access and the socioeconomic milieu in which that access occurs.
Mobile technologies have become an increasingly important component of Africa's evolving health-system infrastructure (Hampshire et al., 2021). Mobile phones can support health information delivery, appointment and treatment reminders, telehealth, patient monitoring, and communication between individuals and health providers (Abane et al., 2021; Hampshire et al., 2021; Mariwah et al., 2022; Owusu, 2024), creating potential pathways through which digital connectivity could reduce temporal, geographic, and informational barriers to care. In Africa, evidence suggests that mobile phone-mediated health interventions can substantially improve aspects of treatment and care, although their implementation and effectiveness depend on the populations reached, the technologies used, and the surrounding health-system context (Opoku et al., 2017). Importantly, the existence of a technological pathway does not answer the question whether individuals with greater digital connectivity are more likely to engage with formal healthcare services.
This distinction is particularly important in Africa, where digital connectivity is growing but remains highly unequal. Although mobile-phone ownership has expanded substantially, access to broadband and mobile internet remains considerably less widespread, and disparities persist across socioeconomic and geographic groups. Afrobarometer data indicate that mobile-phone ownership is substantially more common than mobile internet access across African countries, illustrating that possession of a device does not necessarily translate into meaningful internet and digital connectivity. Yet, research using Afrobarometer data has likewise documented substantial inequalities in mobile-phone ownership across African populations, with implications for the reach of Mobile-Health (mHealth) interventions (Okano et al., 2022). These differences suggest that “digital access” should not be treated as a single construct. Ownership, internet-enabled access, and frequency of use represent distinct dimensions of connectivity that may have different relationships with healthcare behaviour.
This distinction is consistent with broader digital-divide research showing that inequalities extend beyond whether individuals possess or can physically access a digital device. Differences in the resources required to sustain access, digital skills, patterns of use, and the purposes for which technologies are used can persist even as overall connectivity increases (van Deursen & van Dijk, 2019). Consequently, examining mobile-phone ownership alone may obscure potentially important differences in how frequently and functionally people engage with digital technologies. For healthcare, this raises a specific empirical question: does greater mobile connectivity correspond to greater engagement with formal healthcare facilities after accounting for the demographic, socioeconomic, and geographic characteristics that also structure healthcare access?
A further unresolved issue is whether any relationship between digital connectivity and healthcare contact is socially patterned (socio-spatial clustering). Digital technologies may potentially reduce barriers for disadvantaged populations by facilitating access to health information and communication without requiring repeated physical visits to health facilities. Conversely, the benefits of connectivity may be concentrated among people with greater financial resources, education, infrastructure, and digital capabilities. The latter possibility is consistent with the broader digital-divide literature, in which unequal resources can translate into unequal capacity to convert digital access into meaningful outcomes (van Deursen & van Dijk, 2019). Lived poverty, deprivation of five fundamental necessities during the past 12 months, which varies systematically with population sub-groups and geographic locations, therefore provides an important lens through which to examine whether digital connectivity is related to healthcare contact similarly across socioeconomic groups, rather than assuming that an average population-level relationship applies uniformly.
Against this background, we analysed pooled cross-national survey data from five regions in Africa to examine the relationship between mobile connectivity and self-reported contact with a healthcare facility. We addressed four questions. First, are mobile-phone ownership, frequency of phone use, and mobile internet access independently related to healthcare-facility contact after adjustment for demographic, socioeconomic, residential, and regional characteristics? Second, how do these relationships change as covariates and factors are introduced sequentially, thereby assessing the extent to which crude linkages are sensitive to differences in population composition and context? Third, does lived poverty modify the linkage between mobile internet access and healthcare contact? Finally, do substantial regional differences in healthcare contact persist after accounting for individual-level characteristics? By distinguishing multiple dimensions of mobile connectivity and explicitly testing socioeconomic effect modification, this study seeks to clarify whether the expanding digital landscape in Africa is related to healthcare engagement broadly across populations or primarily reflects underlying social and geographic inequalities.
Methods
Data source and study population
We analysed pooled, nationally representative cross-sectional data from Round 8 of the Afrobarometer survey, covering respondents from five African regions: West, Eastern, Northern, Southern, and Central Africa. The analytic sample comprised 44,761 respondents after exclusion of observations with missing data on the outcome, primary exposures, effect modifier, or covariates included in the regression models. Afrobarometer employs standardised survey instruments and nationally representative sampling procedures, enabling cross-national comparison of individual-level experiences, attitudes, and socioeconomic conditions. Because the present analysis uses secondary, de-identified survey data, no additional participant recruitment was undertaken.
Outcome: healthcare-facility contact
The outcome variable was self-reported contact with a public clinic or hospital in the last 12 months, coded as a binary indicator (yes/no). This item was used as an indicator of facility visitation, consistent with Afrobarometer's own interpretation of this item in its published analyses (Afrobarometer, 2025) and with Andersen's Behavioral Model of Health Services Use, in which realized access is operationalised as a binary contact measure of utilisation whether a respondent used (visited) a health facility within a defined recall period (Aday & Andersen, 1974; Andersen & Newman, 1973; Andersen, 1995). This remains a widely applied and current framework in health services research, as confirmed by recent systematic and scoping reviews of its ongoing use (Alkhawaldeh et al., 2023; Lederle et al., 2021). The specific operationalisation used here, self-reported contact with, or visit to, a health facility within the preceding 12 months — mirrors a 2025 application of the model in a comparable West African setting, which defined health service utilisation as “at least one visit to a health facility in the 12 months preceding the study” (Kpolar et al., 2025).
Primary exposures: dimensions of mobile digital inclusion
Three dimensions of phone-based digital inclusion were examined as distinct exposures: mobile-phone ownership, frequency of phone use, and mobile internet access. Mobile-phone ownership was categorised as no household member owns a mobile phone, another household member owns a mobile phone, or the respondent personally owns a mobile phone. Phone-use frequency was categorised into five levels: never, less than monthly, a few times per month, a few times per week, and every day. Mobile internet access was coded dichotomously as no or yes. These indicators were modelled separately but sequentially introduced into the regression models because they represent conceptually distinct dimensions of digital inclusion. Ownership captures basic device access, whereas frequency of use and internet access capture dimensions of engagement and functional connectivity that may not be adequately represented by ownership alone (van Deursen & van Dijk, 2019).
Lived poverty and effect modification
Socioeconomic disadvantage was assessed using the Lived Poverty Index (LPI), an experiential measure developed from respondents' reported frequency of going without basic necessities. The LPI captures material deprivation across domains including food, clean water, medical care, cooking fuel, and cash income (Mattes, 2008; Mattes & Patel, 2022). For the present analysis, lived poverty was classified into four categories: no, low, moderate, and high lived poverty, with no lived poverty specified as the reference category.
We assessed whether lived poverty modified the relationship between mobile internet access and healthcare-facility contact by including product terms between internet access and each of the three poverty categories. Thus, the model estimated whether the relationship between internet access and healthcare contact differed among respondents experiencing low, moderate, or high lived poverty relative to those experiencing no lived poverty. Following standard regression-based approaches to effect-modification analysis (Hayes, 2018), the interaction terms were estimated jointly with the corresponding main effects of internet access and lived poverty.
Factors
All multivariable models included a common set of demographic and contextual covariates: age group (18–24, 25–34, 35–44, 45–54, 55–64, and ≥65 years), sex (male/female), educational attainment (no formal education, primary, secondary, and post-secondary), religion (Christian, Muslim, and other), place of residence (urban/semi-urban versus rural), and African region (West, Eastern, Northern, Southern, and Central Africa). West Africa was specified as the reference region. These variables were selected a priori because they represent established demographic, socioeconomic, and contextual characteristics that may be related to both digital connectivity and healthcare contact.
Statistical analysis
Participant characteristics were summarised using frequencies and percentages (Table 1). Relationships between phone-based digital inclusion and healthcare-facility contact were examined using multivariable binary logistic regression.
Four sequential models were estimated (Table 2). Model 1 included mobile-phone ownership. Model 2 additionally included frequency of phone use. Model 3 further introduced mobile internet access. Model 4 additionally adjusted for age, sex, education, religion, rural/urban residence, and African region. This sequential specification was designed to examine the extent to which relationships between individual dimensions of digital inclusion and healthcare contact changed following adjustment for other dimensions of mobile connectivity and subsequently for demographic and geographic characteristics.
Results are presented as adjusted odds ratios (AORs) with 95% confidence intervals (CIs). For categorical predictors, omnibus tests were used to assess the overall contribution of the categorical variable, with category-specific estimates reported relative to the prespecified reference category. Statistical significance was assessed using two-sided tests with p < 0.05.
A separate multivariable logistic regression model was estimated to assess effect modification by lived poverty (Table 3). This model simultaneously included mobile internet access, lived-poverty categories, the three internet-access × lived-poverty interaction terms, and the full set of demographic and regional covariates. The interaction terms were interpreted as the ratio of the internet-access odds ratio in each poverty category to that in the no-poverty reference group. Consequently, statistical significance of an individual interaction term indicates evidence that the internet-access relationship differs between that poverty category and the reference group.
Importantly, the effect-modification model did not include mobile-phone ownership or frequency of phone use. Accordingly, the internet-access coefficient in Table 3 represents a different model specification from the corresponding coefficient in Table 2 Model 4 and should not be interpreted as a direct test of attenuation following the addition of lived poverty and interaction terms. The effect-modification analysis was instead treated as a distinct model addressing whether the internet-access relationship varied across levels of lived poverty.
Model adequacy was assessed using the −2 log-likelihood, Cox and Snell R², Nagelkerke R², and Hosmer-Lemeshow goodness-of-fit test. Because the Hosmer–Lemeshow statistic can be sensitive to large sample sizes, its results were interpreted alongside the other model diagnostics rather than as a standalone criterion of model adequacy. Given the cross-sectional design, all regression estimates were interpreted as relationships rather than causal effects.
All analyses were conducted using IBM SPSS Statistics version 22.
Geospatial Analysis
Geospatial analysis was conducted in ArcGIS (v10.8; Esri Inc., Redlands, CA, USA). Three national-level survey indicators, namely Mobile Phone Ownership, Internet Access, and Contact with a Health Facility, each expressed as a country-level proportion of survey respondents, were used. Country-level Lived Poverty Index (LPI) scores were extracted from the survey dataset and ranked in ascending order to characterize the continental distribution of lived poverty. The ranked scores were subsequently partitioned into quartile groups, representing the bottom 25th percentile (low poverty), the interquartile range (moderate poverty), and the top 75th percentile (high poverty). Indicator estimates were joined to a georeferenced polygon shapefile of African national boundaries via a standardized attribute table, enabling spatial linkage between statistical estimates and their corresponding administrative units. Choropleth mapping was applied to visualize each indicator, with data classified into five classes using the Natural Breaks (Jenks) method to minimize intra-class variance and maximize inter-class differences, ensuring class boundaries aligned with empirically meaningful discontinuities in the data distribution. From this same country-level LPI scores, each quartile was mapped separately with five graduated intervals and rendered using a sequential colour scheme of increasing poverty intensity. The resulting cartographic outputs enabled comparative assessment of sub-regional poverty clustering and spatial differentiation in the distribution of digital access, healthcare contact, and lived poverty across the study area.
Results
Sample Characteristics
The analytic sample comprised 44,761 respondents (Table 1). The sample was balanced by sex (49.7% female) and 54% was rural. Respondents aged 25-34 years constituted the largest age group (29.3%), followed by those aged 18-24 years (21.9%) and 35-44 years (21.0%). West Africa contributed 39.0% of respondents and Eastern Africa 29.9%, with smaller contributions from Southern (12.9%), Central (9.4%), and Northern Africa (8.9%).
Mobile phone access was widespread: 83.6% of respondents personally owned a mobile phone and 78.8% reported using a phone daily. In contrast, mobile internet access was reported by 51.6%. More than half of respondents (52.2%) never obtained news through social media. Overall, 61.1% reported contact with a public clinic or hospital.
Spatial Distribution of Mobile Phone Ownership, Internet Connectivity and Health Facility Contact Across Africa
Choropleth visualization of the three national-level indicators revealed a generally positive yet spatially heterogeneous relationship between mobile connectivity and healthcare access across Africa (Figure 1, Figure 2 and Figure 3). Mobile Phone Ownership (Figure 1) shows the greatest geographic diffusion among the indicators mapped, with larger ownership rates recorded across a substantial proportion of African nations notwithstanding comparatively limited internet penetration. Larger proportions of respondents in North and Southern African nations, including Morocco, Tunisia, and South Africa, owned a mobile phone and had access to mobile phone internet (Figure 2), consistent with more advanced telecommunications infrastructure and higher socioeconomic development indices in these subregions. Conversely, extensive zones across the Sahel, West Africa, and parts of East Africa were classified within the lowest Natural Breaks tiers for Internet Access (Figure 2), indicating the gap between mobile phone ownership and access to internet.
The relationship between digital connectivity and Contact with a Health Facility (Figure 1, Figure 2 and Figure 3) exhibited considerable complexity at the national level. While countries such as Senegal and Kenya showed spatial correspondence between higher internet access and higher health facility contact, South Africa presented a notable divergence, indicating that health-seeking behaviour is mediated by additional structural determinants beyond digital access, including infrastructure capacity, service affordability, and sociocultural factors.
Spatial Distribution of Lived Poverty
Figure 4 reveals pronounced spatial heterogeneity in lived poverty across the study countries, with sub-regional clustering consistent with a north-south poverty gradient. Countries in the lowest quartile (LPI: 13.0–46.0) are concentrated in North Africa, while West Africa exhibits moderate deprivation levels (85.1–204.0), with isolated high-intensity outliers (365.1–591.0). The middle quartile (LPI: 78.0–827.0) spans the widest geographic range but is dominated by an East African high-poverty cluster, where contiguous countries record values of 527.1–827.0, indicative of spatially correlated deprivation driven by shared structural vulnerabilities. Southern Africa occupies the lower end of this tier. The highest quartile (LPI: 31.0–650.0) is overwhelmingly concentrated in Central and East Africa, with Angola recording peak deprivation (444.1–650.0), forming a contiguous high-poverty corridor across the continent's interior. Collectively, the maps delineate a coherent continental poverty architecture in which North Africa anchors the lowest tier, East and Central Africa constitute the high-poverty core, and West and Southern Africa occupy intermediate positions.
Sequential logistic regression of phone-based digital inclusion and healthcare contact
Table 2 presents the sequential logistic regression models. The relationship between mobile phone ownership and healthcare-facility contact was not statistically significant in the initial model (Model 1; overall p>0.05). After frequency of phone use was added, ownership became significant overall (Model 2; p = .016), although the relationship was confined to personal ownership, which was related to lower odds of contact relative to households in which no member owned a phone (AOR 0.898, 95% CI 0.811–0.994; p<0.05). A similar relationship was observed after additionally accounting for internet access (Model 3; AOR 0.886, 95% CI 0.800–0.980; p = .019). However, following adjustment for demographic and geographic characteristics, the overall relationship was no longer statistically significant (Model 4; p>0.05), and the estimate for personal ownership was close to the null (AOR 1.054, 95% CI 0.950–1.170).
Frequency of phone use showed a more consistent relationship with healthcare contact than ownership. The overall relationship remained statistically significant across Models 2–4 (p<0.05, <0.05, and <.001, respectively). In the fully adjusted model, respondents using a phone few times per week had higher odds of contact than those who never used a phone (AOR 1.136, 95% CI 1.013–1.273), as did daily users (AOR 1.217, 95% CI 1.091–1.357). Conversely, use of a phone less than once a month was related to lower odds of contact (AOR 0.837, 95% CI 0.709–0.988). The category-specific estimates therefore suggest a stronger relationship between intensity of phone use and healthcare contact than between phone ownership per se and contact.
The relationship for mobile internet access varied substantially across model specifications. In Model 3, internet access was related to lower odds of healthcare contact (AOR 0.850, 95% CI 0.818–0.883; p < .001). After further adjustment for age, sex, education, religion, residence, and region, the direction of relationship reversed, with internet access related to higher odds of contact (Model 4: AOR 1.081, 95% CI 1.033–1.131; p = .001). This change in magnitude and direction indicates that the estimated relationship was sensitive to adjustment for sociodemographic and geographic characteristics.
Several covariates were strongly related to healthcare contact in Model 4. Odds increased progressively with age, from AOR 1.257 (95% CI 1.190-1.327) among respondents aged 25-34 years to 1.577 (95% CI 1.433-1.735) among those aged ≥65 years, relative to those aged 18-24 years (overall p < .001). Women had higher odds of contact than men (AOR 1.338, 95% CI 1.286-1.392; p < .001). Education was significant overall (p < .001), although the direction varied by level: primary education was related to higher odds (AOR 1.071, 95% CI 1.006-1.140), whereas secondary (AOR 0.908, 95% CI 0.851-0.969) and post-secondary education (AOR 0.808, 95% CI 0.748-0.873) were related to lower odds relative to no formal education. Rural residence was related to higher odds of contact (AOR 1.143, 95% CI 1.095-1.193).
Substantial regional heterogeneity was also observed (overall p < .001). Relative to West Africa, respondents in Eastern Africa had higher odds of contact (AOR 1.362, 95% CI 1.293-1.435), whereas those in Northern Africa had markedly lower odds (AOR 0.411, 95% CI 0.380-0.444). Southern and Central Africa did not differ significantly from West Africa.
Model fit improved as covariates were added, with -2 log-likelihood decreasing from 59,807.828 in Model 1 to 58,337.164 in Model 4 and Nagelkerke R² increasing from approximately zero in Models 1–2 to 0.044 in Model 4. The Hosmer–Lemeshow test was significant in Models 3 and 4 (p = .003 and .022, respectively), indicating some departure from ideal calibration.
Interaction analysis: Internet access and lived poverty
Table 3 evaluates whether the relationship between mobile internet access and healthcare-facility contact varied according to lived poverty. This model is a separate specification from Model 4 in Table 2: it includes lived poverty and the internet-access interaction terms but does not include mobile phone ownership or frequency of phone use. Consequently, estimates from Table 3 should not be interpreted as a direct extension of, or compared numerically with, Model 4 in Table 2.
Within the no-lived-poverty reference category, mobile internet access was not significantly related to healthcare contact (AOR 1.074, 95% CI 0.947-1.218; p = .263). The interaction estimates provided no evidence of substantial heterogeneity across poverty categories. The interaction between internet access and low lived poverty was AOR 1.043 (95% CI 0.907-1.200; p = .553), compared with no lived poverty; corresponding estimates were 1.005 (95% CI 0.873-1.157; p = .943) for moderate lived poverty and 1.021 (95% CI 0.879-1.185; p = .789) for high lived poverty.
Taken together, the individual interaction terms did not provide statistical evidence that lived poverty modified the relationship between internet access and healthcare contact. This finding should be interpreted cautiously, however, because the absence of statistically significant interaction terms does not demonstrate that the relationships are identical across poverty groups; rather, the data did not provide evidence of statistically detectable heterogeneity under this model specification.
In contrast, lived poverty itself was strongly related to healthcare contact (overall p < .001). Compared with respondents reporting no lived poverty, odds of contact were higher among those experiencing low (AOR 1.418, 95% CI 1.267-1.587), moderate (AOR 1.709, 95% CI 1.528-1.911), and high lived poverty (AOR 1.646, 95% CI 1.466-1.849; all p < .001). The strongest relationship was observed for moderate lived poverty.
The relationships of age, sex, residence, and region were broadly consistent with those observed in Model 4. Older age and female sex were related to higher odds of contact, as was rural residence. Regional heterogeneity remained pronounced: relative to West Africa, odds were higher in Eastern Africa (AOR 1.351, 95% CI 1.283-1.423) and lower in Northern Africa (AOR 0.437, 95% CI 0.404–0.472) and Central Africa (AOR 0.860, 95% CI 0.798–0.926).
The interaction model had a Nagelkerke R² of 0.050 and a −2 log-likelihood of 58,142.267. The Hosmer–Lemeshow test was significant (χ² = 28.381, df = 8; p < .001), indicating imperfect calibration.
Importantly, the internet-access estimate in Table 3 should not be interpreted as an attenuation of the positive relationship observed in Model 4. Internet access was related to higher odds of contact in Model 4 (AOR 1.081, 95% CI 1.033-1.131), but was not statistically significant in Table 3 (AOR 1.074, 95% CI 0.947-1.218). Because Table 3 removes phone ownership and frequency of phone use and simultaneously introduces lived poverty and three interaction terms, the two estimates arise from different model specifications. The difference therefore cannot be attributed specifically to lived poverty or effect modification.
In the effect-modification model (Table 3), mobile phone internet access was not significantly related to contact with a clinic or hospital (OR 1.074, 95% CI 0.947-1.218; p=.263), and there was no evidence that this relationship differed by lived-poverty status, with interaction estimates close to the null for low (OR 1.043, 95% CI 0.907-1.200; p=.553), moderate (OR 1.005, 95% CI 0.873-1.157; p=.943), and high lived poverty (OR 1.021, 95% CI 0.879-1.185; p=.789). Thus, lived poverty did not appear to modify the relationship between internet access and healthcare contact. In contrast, lived poverty itself was strongly related to healthcare contact (omnibus p<.001): compared with respondents experiencing no lived poverty, the odds of contact were higher among those experiencing low (OR 1.418, 95% CI 1.267-1.587), moderate (OR 1.709, 95% CI 1.528-1.911), and high lived poverty (OR 1.646, 95% CI 1.466-1.849; all p<.001). The demographic pattern was broadly consistent with the preceding models, with progressively higher odds of healthcare contact across older age groups, reaching OR 1.617 (95% CI 1.469-1.780; p<.001) among those aged ≥65 years versus 18-24 years; women had higher odds than men (OR 1.332, 95% CI 1.281-1.386; p<.001), and rural residents had modestly higher odds than urban residents (OR 1.075, 95% CI 1.030-1.122; p=.001). Regional disparities were also pronounced, with higher odds of contact in Eastern Africa (OR 1.351, 95% CI 1.283-1.423) and lower odds in Northern Africa (OR 0.437, 95% CI 0.404-0.472) and Central Africa (OR 0.860, 95% CI 0.798-0.926) relative to West Africa (omnibus p<.001). Notably, although internet access was positively related to healthcare contact in the fully adjusted model in Table 2 (OR 1.081, 95% CI 1.033-1.131; p=.001), this relationship was not statistically significant in Table 3; because the Table 3 specification does not include the phone-ownership and frequency-of-use variables included in Table 2, this attenuation should not be interpreted as being attributable solely to adjustment for lived poverty or the interaction terms.
Discussion
This study examined whether three dimensions of phone-based digital inclusion: mobile phone ownership, phone-based internet access, and frequency of phone use were independently related to self-reported contact with a public clinic or hospital across five African regions, and whether lived poverty modified the relationship between internet access and healthcare contact. Four findings merit particular attention. First, adjustment substantially altered the estimated relationship between internet access and healthcare contact. Second, frequency of phone use was more consistently related to healthcare contact than phone ownership, while internet access became positively related only after fuller adjustment. Third, lived poverty did not modify the internet access-health facility contact relationship despite having an independent relationship with healthcare contact. Fourth, substantial regional heterogeneity persisted, with regional differences exceeding the magnitude of most individual-level digital-inclusion relationships.
Digital inclusion and the importance of adjustment
The sequential models provide evidence that the apparent relationship between digital inclusion and healthcare contact is highly sensitive to covariate adjustment. Most notably, the relationship between phone-based internet access and healthcare contact changed from negative in the less-adjusted model (AOR = 0.850) to positive after adjustment for demographic and regional characteristics (AOR = 1.081). Although this coefficient reversal should not be interpreted as definitive proof of a particular causal mechanism, it is consistent with substantial confounding or statistical suppression by characteristics correlated with both internet access and healthcare contact. Younger age, urban residence, education, and geographic location are plausible contributors because digital connectivity is socially patterned, while healthcare utilisation is likewise structured by demographic, socioeconomic, and geographic conditions. Research on digital inequality similarly shows that internet access, patterns of use, and the benefits derived from use are deeply embedded in existing social inequalities rather than operating independently of them (Scheerder et al., 2017).
This finding has an important methodological implication. Relationships between digital connectivity and health behaviours should not be interpreted from crude or minimally adjusted models simply because the digital variable itself is statistically significant. In contexts such as Africa, where connectivity, education, urbanisation, socioeconomic position, and healthcare access are strongly patterned across populations, inadequate adjustment can produce estimates that substantially misrepresent the direction or magnitude of a relationship. Afrobarometer's sampling framework itself recognises the importance of geographic and population structure in cross-national estimation, with national samples designed to represent adult populations across urban and rural settings.
Importantly, the reversal observed here should not be described as evidence that internet access causes greater healthcare contact. The cross-sectional design prevents establishing temporal ordering, and residual confounding remains possible. Rather, the finding indicates that the crude relationship between connectivity and healthcare contact differs materially from the relationship observed after accounting for measured demographic and geographic characteristics.
Access is not equivalent to use
A second important finding is the divergence between phone ownership, internet access, and frequency of phone use. Phone ownership did not retain an independent relationship with healthcare contact in the fully adjusted model, whereas frequency of phone use showed the most consistent relationship across the model sequence. Internet access occupied an intermediate position, becoming positively related to healthcare contact only after full adjustment.
This pattern is consistent with the broader digital-divide literature, which increasingly distinguishes physical access to technology from how technology is used and the outcomes generated through that use. Van Deursen and van Dijk argue that digital inequality extends beyond simple physical access to differences in material access, skills, types of use, and opportunities to derive benefits from technology (van Deursen & van Dijk, 2019). Similarly, a systematic review of the second- and third-level digital divide found that digital inequalities increasingly concern differences in internet skills, types of use, and the outcomes individuals obtain from internet engagement rather than access alone (Scheerder et al., 2017).
Our findings extend this conceptual distinction to healthcare contact in a large African cross-national sample. Possessing a mobile phone may indicate little more than potential connectivity. It does not establish whether the device is regularly used, whether the individual has affordable and reliable internet access, whether they possess the skills required to find and evaluate health information, or whether digital engagement translates into a concrete healthcare-related action. Frequency of use may therefore capture a dimension of digital engagement that ownership cannot. The stronger and more consistent relationship observed for phone-use frequency is consequently compatible with a pathway in which repeated engagement with mobile technologies creates more opportunities to seek information, communicate with providers or social networks, navigate services, or respond to health needs.
However, frequency of use should not itself be interpreted as evidence of effective or health-oriented use. Digital-divide research indicates that individuals differ not only in whether they use the internet but also in the purposes, skills, and benefits related to that use (Scheerder et al., 2017). Future surveys should therefore move beyond binary measures of ownership and access towards measures of type, intensity, purpose, affordability, skills, and health-related use. This distinction is particularly relevant to digital-health policy: the existence of a mobile connection does not necessarily imply that a person can convert that connection into improved access to healthcare.
Lived poverty and the absence of effect modification
Contrary to a hypothesis that socioeconomic disadvantage might alter the capacity to translate internet access into healthcare contact, none of the poverty × internet-access interaction terms was statistically significant. The data therefore provide no evidence that the relationship between internet access and healthcare contact differed systematically across levels of lived poverty.
This finding is narrower than an assertion that digital technologies operate equally across socioeconomic groups. Digital inequality research suggests that socioeconomic advantage can shape internet skills, patterns of use, and the benefits obtained from digital engagement (Scheerder et al., 2017). The absence of statistical interaction in the present study may therefore indicate that the particular outcome examined (contact with a public clinic or hospital) is influenced by constraints that are not adequately captured by internet access alone. For example, internet access may facilitate information acquisition or communication without overcoming transport costs, facility availability, waiting times, service affordability, or perceived quality of care.
The finding is also important because lived poverty itself remained independently related to healthcare contact. Thus, poverty appears to matter for healthcare contact without statistically conditioning the estimated relationship between internet access and contact. This pattern is more consistent with additive rather than multiplicative heterogeneity in the present data. Nevertheless, the absence of interaction should not be interpreted as evidence of equality across poverty groups: statistical non-significance may also reflect limited power to detect interaction, particularly when interaction effects are smaller than main effects.
From a policy perspective, the implication is therefore not that poverty can be ignored when implementing digital-health interventions. Rather, the results suggest that poverty-targeted differentiation of an intervention solely on the assumption that internet access will have a stronger or weaker relationship with healthcare contact among poorer individuals is not supported by these data. Digital interventions should instead be embedded within broader strategies addressing the material and structural barriers that shape healthcare utilisation.
Regional heterogeneity may be more consequential than individual digital access
The magnitude of the regional coefficients provides perhaps the strongest contextual signal in the analysis. Relative to West Africa, respondents in Northern Africa had approximately 56-59% lower adjusted odds of healthcare contact (AOR = 0.41-0.44), whereas respondents in Eastern Africa had approximately 35-36% higher odds (AOR = 1.35-1.36). These differences are substantially larger than most individual-level relationships involving the digital-inclusion variables.
Such regional heterogeneity is consistent with evidence that health-service utilisation across Africa is strongly patterned by socioeconomic position, place of residence, geography, and other contextual characteristics. A recent scoping review of 178 studies found substantial inequalities in health-service coverage across African populations, with particularly consistent differences by socioeconomic status, urban–rural residence, and region (Karamagi et al., 2024). Regional differences may reflect variation in health-system capacity, facility availability, workforce distribution, financing arrangements, insurance coverage, transport infrastructure, epidemiological needs, and sociocultural patterns of care-seeking. Health-system efficiency and capacity also vary considerably across African settings (Nabyonga-Orem et al., 2023).
These mechanisms, however, cannot be distinguished in the present analysis. Region is an ecological proxy rather than a direct measure of health-system performance, and interpreting the coefficients as evidence that particular health-system characteristics caused the observed differences would exceed what the data support. Nevertheless, the size and persistence of the regional relationships suggest that individual-level digital inclusion should not be considered in isolation. Digital connectivity operates within health systems whose accessibility and responsiveness may ultimately determine whether digital engagement translates into actual facility contact.
Implications for digital-health research and policy
Several implications follow. First, studies examining digital inclusion and healthcare utilisation should routinely distinguish between ownership, connectivity, use, and realised health benefits rather than treating them as interchangeable indicators. The present findings demonstrate empirically that these measures can produce different conclusions within the same population.
Second, adjustment for demographic and geographic structure is particularly important in cross-national African analyses. The reversal of the internet-access coefficient demonstrates that statistical significance in an unadjusted model can be substantively misleading. Future analyses should also consider whether country-level or subnational contextual variables account for some of the regional heterogeneity observed here.
Third, the results support a shift from access-centred to use- and outcome-centred digital-health measurement. WHO guidance recognises the potential of digital interventions to strengthen health systems, including in lower-resource settings, but their effectiveness depends on how interventions are implemented within existing health-system structures (World Health Organization, 2019). For population surveys, this means collecting information not only on whether individuals own a phone or access the internet but also on whether they use digital technologies to search for health information, communicate with health workers, schedule or navigate services, obtain referrals, manage treatment, or overcome specific barriers to care.
Fourth, the strong regional gradients suggest that digital-health interventions are unlikely to substitute for investments in conventional health-system capacity. Connectivity can potentially facilitate navigation and communication, but it cannot by itself compensate for inadequate facility availability, financial barriers, geographical isolation, or shortages of health workers. Evidence on health-service inequalities across Africa similarly indicates that digital solutions should be considered alongside broader structural determinants of service utilisation rather than as stand-alone solutions (Karamagi et al., 2024).
Policy Implications of Lived Poverty, Digital Access, and Health Facility Utilization
Across West and Central Africa, mobile phone ownership consistently outpaces internet access, showing that device penetration alone does not guarantee connectivity closing this gap through lower data costs and low-bandwidth services is a clear policy lever. Morocco and Tunisia's combination of high ownership, high connectivity, and lower poverty suggests sustained infrastructure investment can break this cycle elsewhere in the region. Where poverty, weak connectivity, and low facility contact coincide, as in parts of West Africa, digital health interventions will have limited reach until connectivity improves; by contrast, high facility contact despite high poverty in parts of Central and East Africa points to community health worker networks and donor-supported programs sustaining utilization independent of digital access. Digital infrastructure should therefore be treated as integral to health systems strengthening rather than a separate sectoral priority, with connectivity, low-bandwidth mHealth, and digital literacy addressed in sequence.
Limitations
First, the cross-sectional design precludes causal inference. Phone ownership, internet access, phone-use frequency, lived poverty, and healthcare contact were measured contemporaneously, so temporal ordering cannot be established. The sequential changes in regression coefficients are therefore informative about the sensitivity of relationships to adjustment but do not establish causal pathways or prove the presence of a particular confounding mechanism.
Second, Table 2 and Table 3 represent different model specifications. Table 3 excludes phone ownership and phone-use frequency; consequently, the difference in the significance of internet access between the two tables cannot be attributed solely to the introduction of lived poverty and the interaction terms. The estimates should therefore be interpreted within their respective specifications rather than as a simple sequential test of the effect of adding poverty.
Third, model fit was modest, with Nagelkerke R² values of up to 0.044 in Table 2 and 0.050 in Table 3. The significant Hosmer-Lemeshow tests in the more complex models (Table 2 Models 3-4, p ≤ 0.022; Table 3, p < 0.001) further indicate limitations in calibration. Accordingly, the models should be viewed primarily as estimating relationships between covariates and the odds of reported facility contact rather than as high-performing predictive models.
Fourth, several relationships were non-monotonic. Moderate lived poverty, for example, showed a larger relationship with contact than high lived poverty, while the education coefficients did not follow a simple linear gradient. These patterns should not be retrospectively rationalised without supporting evidence. They may reflect heterogeneous healthcare needs, measurement characteristics, residual confounding, selection effects, or other mechanisms that cannot be distinguished with the available cross-sectional data.
Fifth, the principal measures were self-reported and may be affected by recall error, reporting differences, or social desirability bias. Such measurement error may attenuate relationships or introduce differential error if reporting varies systematically across demographic or socioeconomic groups.
Finally, generalisability should be interpreted within the countries and survey period represented in the five regional groups. Afrobarometer Round 8 comprises nationally representative surveys conducted across participating African countries, but a regional grouping does not represent a random sample of all countries within a geographic region. The regional estimates should therefore be understood as relationships within the countries included in this analysis rather than definitive estimates for Northern, Eastern, Western, or other African regions as geographical entities.
Conclusion
In this large pooled cross-national sample, the relationship between phone-based digital inclusion and healthcare contact depended strongly on how digital inclusion was operationalised and how confounding was addressed. Frequency of phone use showed the most consistent independent relationship with healthcare contact, whereas phone ownership was not independently related to contact after full adjustment. Phone-based internet access displayed a particularly important modelling sensitivity, changing from a significant negative relationship in a less-adjusted model to a modest positive relationship after adjustment for demographic and regional characteristics. This finding underscores the importance of distinguishing crude digital-access gradients from independently estimated relationships.
Lived poverty remained independently related to healthcare contact but did not statistically modify the internet access-contact relationship, providing no evidence that the relationship between internet access and facility contact differed across poverty levels. At the same time, the pronounced regional gradients, particularly the substantially lower odds of contact in Northern Africa and higher odds in Eastern Africa relative to West Africa, indicate that contextual factors may be at least as consequential as individual-level digital characteristics.
Taken together, these findings argue against conceptualising digital inclusion simply as whether an individual owns or can access a phone. For healthcare, the more consequential question may be whether individuals regularly and meaningfully use digital technologies in ways that can be translated into engagement with health services. Future research should therefore move beyond ownership measures towards multidimensional assessments of connectivity, frequency and purpose of use, digital skills, affordability, health-related digital engagement, acceptability of digital health among healthcare practitioners and realised health benefits, while simultaneously accounting for the health-system and regional contexts in which digital technologies operate.
References
- Abane, A. M.; Mariwah, S.; Owusu, S. A.; Kasim, A.; Robson, E.; Hampshire, K. Mobile phone use and the welfare of community health nurses in Ghana: An analysis of unintended costs. World Dev. Perspect. 2021, 23, 100317. [Google Scholar] [CrossRef]
- Aday, L. A.; Andersen, R. A framework for the study of access to medical care. Health Serv. Res. 1974, 9(3), 208–220. [Google Scholar] [PubMed]
- Afrobarometer. Struggling to obtain quality health care: Malawians look to government to ensure access (Dispatch No. 1040). 2025. Available online: https://www.afrobarometer.org/wp-content/uploads/2025/09/AD1040-Struggling-to-obtain-quality-health-care-Malawians-look-to-govt-to-ensure-access-Afrobarometer-5sept25.pdf.
- Alkhawaldeh, A.; M, A. L.; Rayan, A.; Abdalrahim, A.; Musa, A.; Eshah, N.; S, A. L. Application and Use of Andersen's Behavioral Model as Theoretical Framework: A Systematic Literature Review from 2012-2021. Iran. J. Public Health 2023, 52(7), 1346–1354. [Google Scholar] [CrossRef] [PubMed]
- Andersen, R.; Newman, J. F. Societal and individual determinants of medical care utilization in the United States. Milbank Mem. Fund. Q. Health Soc. 1973, 51(1), 95–124. [Google Scholar] [CrossRef]
- Andersen, R. M. Revisiting the behavioral model and access to medical care: does it matter? J. Health Soc. Behav. 1995, 36(1), 1–10. [Google Scholar] [CrossRef]
- Dawkins, B.; Renwick, C.; Ensor, T.; Shinkins, B.; Jayne, D.; Meads, D. What factors affect patients' ability to access healthcare? An overview of systematic reviews. Trop. Med. Int. Health 2021, 26(10), 1177–1188. [Google Scholar] [CrossRef] [PubMed]
- Hampshire, K.; Mwase-Vuma, T.; Alemu, K.; Abane, A.; Munthali, A.; Awoke, T.; Kasim, A. Informal mhealth at scale in Africa: Opportunities and challenges. World Dev. 2021, 140, 105257. [Google Scholar] [CrossRef]
- Hayes, A. F. Introduction to Mediation, Moderation, and Conditional Process Analysis: A Regression-Based Approach (Methodology in the Social Sciences), 2nd ed ed.; The Guilford Press, 2018. [Google Scholar]
- Karamagi, H. C.; Afriyie, D. O.; Ben Charif, A.; Sy, S.; Kipruto, H.; Moyo, T.; Droti, B. Mapping inequalities in health service coverage in Africa: a scoping review. BMJ Open 2024, 14(11), e082918. [Google Scholar] [CrossRef] [PubMed]
- Kpolar, O. Y. W.; Attafuah, P. Y. A.; Tornu, E.; Senoo-Dogbey, V. E.; Arhinful, D. K. Factors influencing health service utilisation among older adults in the Tamale metropolis: a cross-sectional study based on Andersen's behavioural model. BMC Geriatr. 2025, 25(1), 937. [Google Scholar] [CrossRef] [PubMed]
- Lederle, M.; Tempes, J.; Bitzer, E. M. Application of Andersen's behavioural model of health services use: a scoping review with a focus on qualitative health services research. BMJ Open 2021, 11(5), e045018. [Google Scholar] [CrossRef] [PubMed]
- Mariwah, S.; Machistey Abane, A.; Asiedu Owusu, S.; Kasim, A.; Robson, E.; Castelli, M.; Hampshire, K. Formalising ‘informal’ mHealth in Ghana: Opportunities and challenges for Universal Health Coverage (UHC). Glob. Public Health 2022, 17(5), 768–781. [Google Scholar] [CrossRef] [PubMed]
- Mattes, R. The material and political bases of lived poverty in Africa: Insights from the Afrobarometer. In Afrobarometer Working Paper No. 98.; 2008; Available online: https://www.afrobarometer.org/publication/wp98-material-and-political-bases-lived-poverty-africa-insights-afrobarometer/.
- Mattes, R.; Patel, J. Lived poverty resurgent: COVID-19 restrictions feed economic contraction to drive down living standards in Africa Afrobarometer Policy Paper No. 84.; 2022; Available online: https://www.afrobarometer.org/publication/pp84-lived-poverty-resurgent/.
- Nabyonga-Orem, J.; Christmal, C.; Addai, K. F.; Mwinga, K.; Aidam, K.; Nachinab, G.; Asamani, J. A. The state and significant drivers of health systems efficiency in Africa: A systematic review and meta-analysis. J. Glob. Health 2023, 13, 04131. [Google Scholar] [CrossRef] [PubMed]
- Okano, J. T.; Ponce, J.; Krönke, M.; Blower, S. Lack of ownership of mobile phones could hinder the rollout of mHealth interventions in Africa. Elife 2022, 11. [Google Scholar] [CrossRef] [PubMed]
- Opoku, D.; Stephani, V.; Quentin, W. A realist review of mobile phone-based health interventions for non-communicable disease management in sub-Saharan Africa. BMC Med. 2017, 15(1), 24. [Google Scholar] [CrossRef] [PubMed]
- Owusu, S. A. Ethical implications of the widespread use of informal mHealth methods in Ghana. J. Med. Ethics 2024, 50(8), 563–568. [Google Scholar] [CrossRef] [PubMed]
- Scheerder, A.; van Deursen, A.; van Dijk, J. Determinants of Internet skills, uses and outcomes. A systematic review of the second- and third-level digital divide. Telemat. Inform. 2017, 34(8), 1607–1624. [Google Scholar] [CrossRef]
- van Deursen, A. J.; van Dijk, J. A. The first-level digital divide shifts from inequalities in physical access to inequalities in material access. New Media Soc. 2019, 21(2), 354–375. [Google Scholar] [CrossRef] [PubMed]
- World Health Organization. Recommendations on digital interventions for health system strengthening – Evidence and recommendations. 2019. Available online: https://iris.who.int/server/api/core/bitstreams/0d2bf963-9eaa-4076-be82-9c54190093fc/content.
Figure 1.
Spatial distribution of national-level Mobile Phone Ownership across study countries.
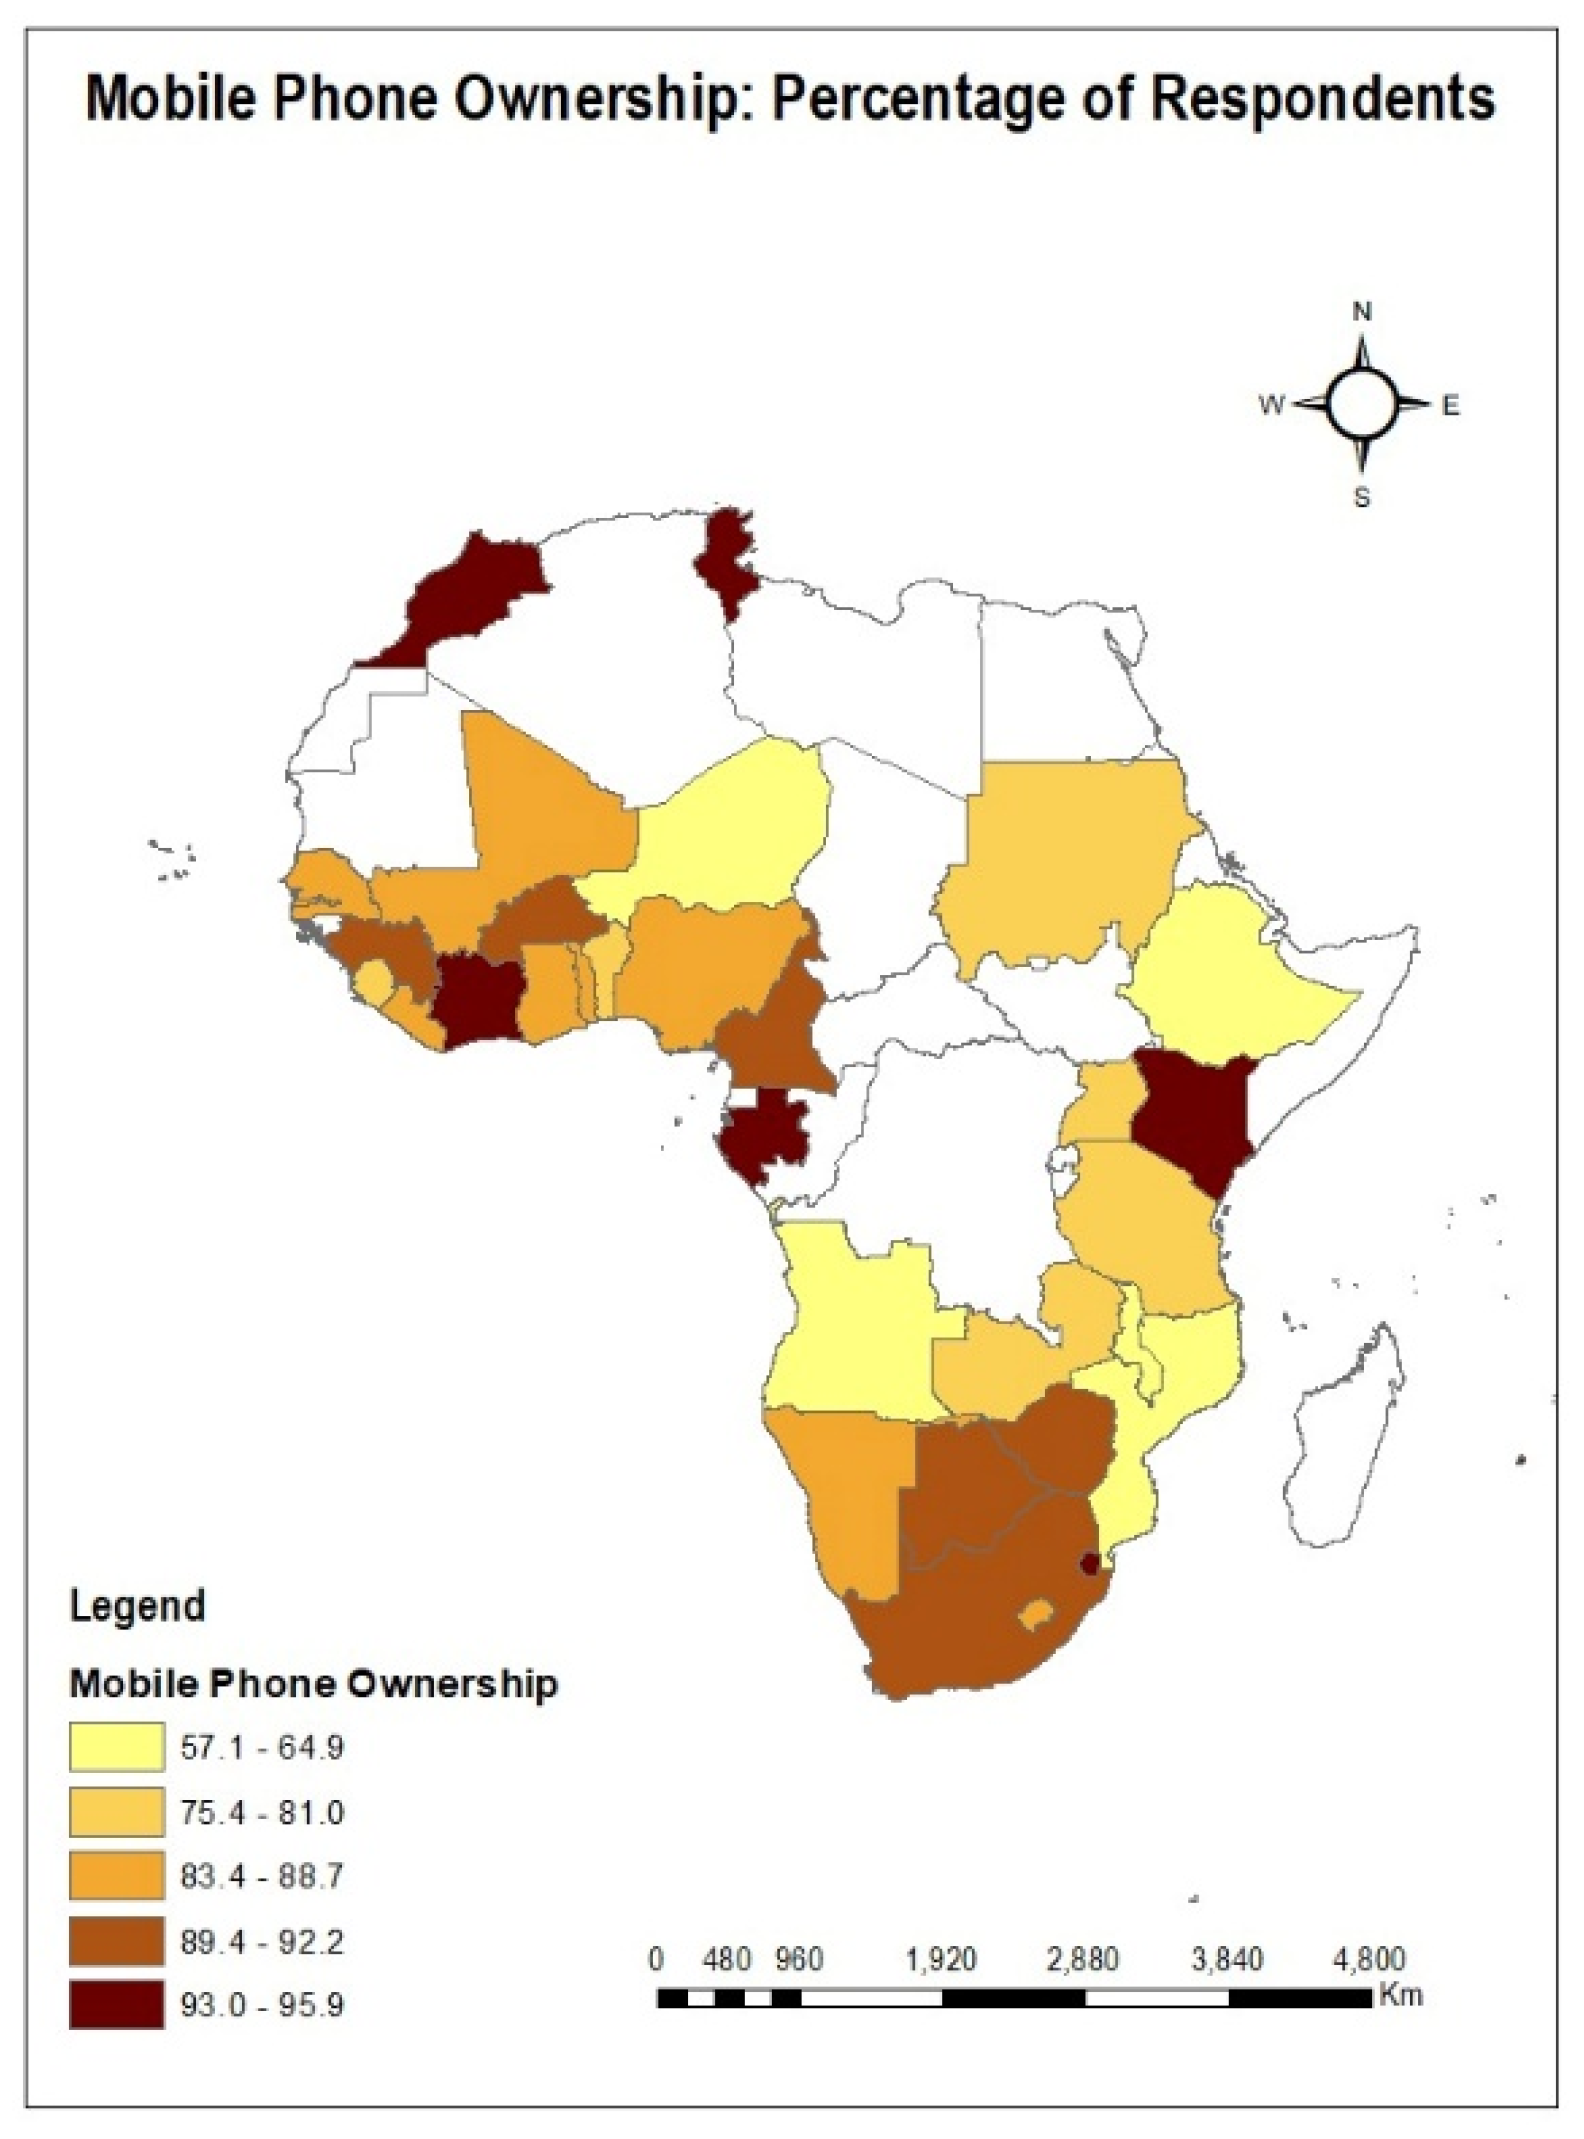
Figure 2.
Spatial distribution of Mobile phone Internet Access across study countries.
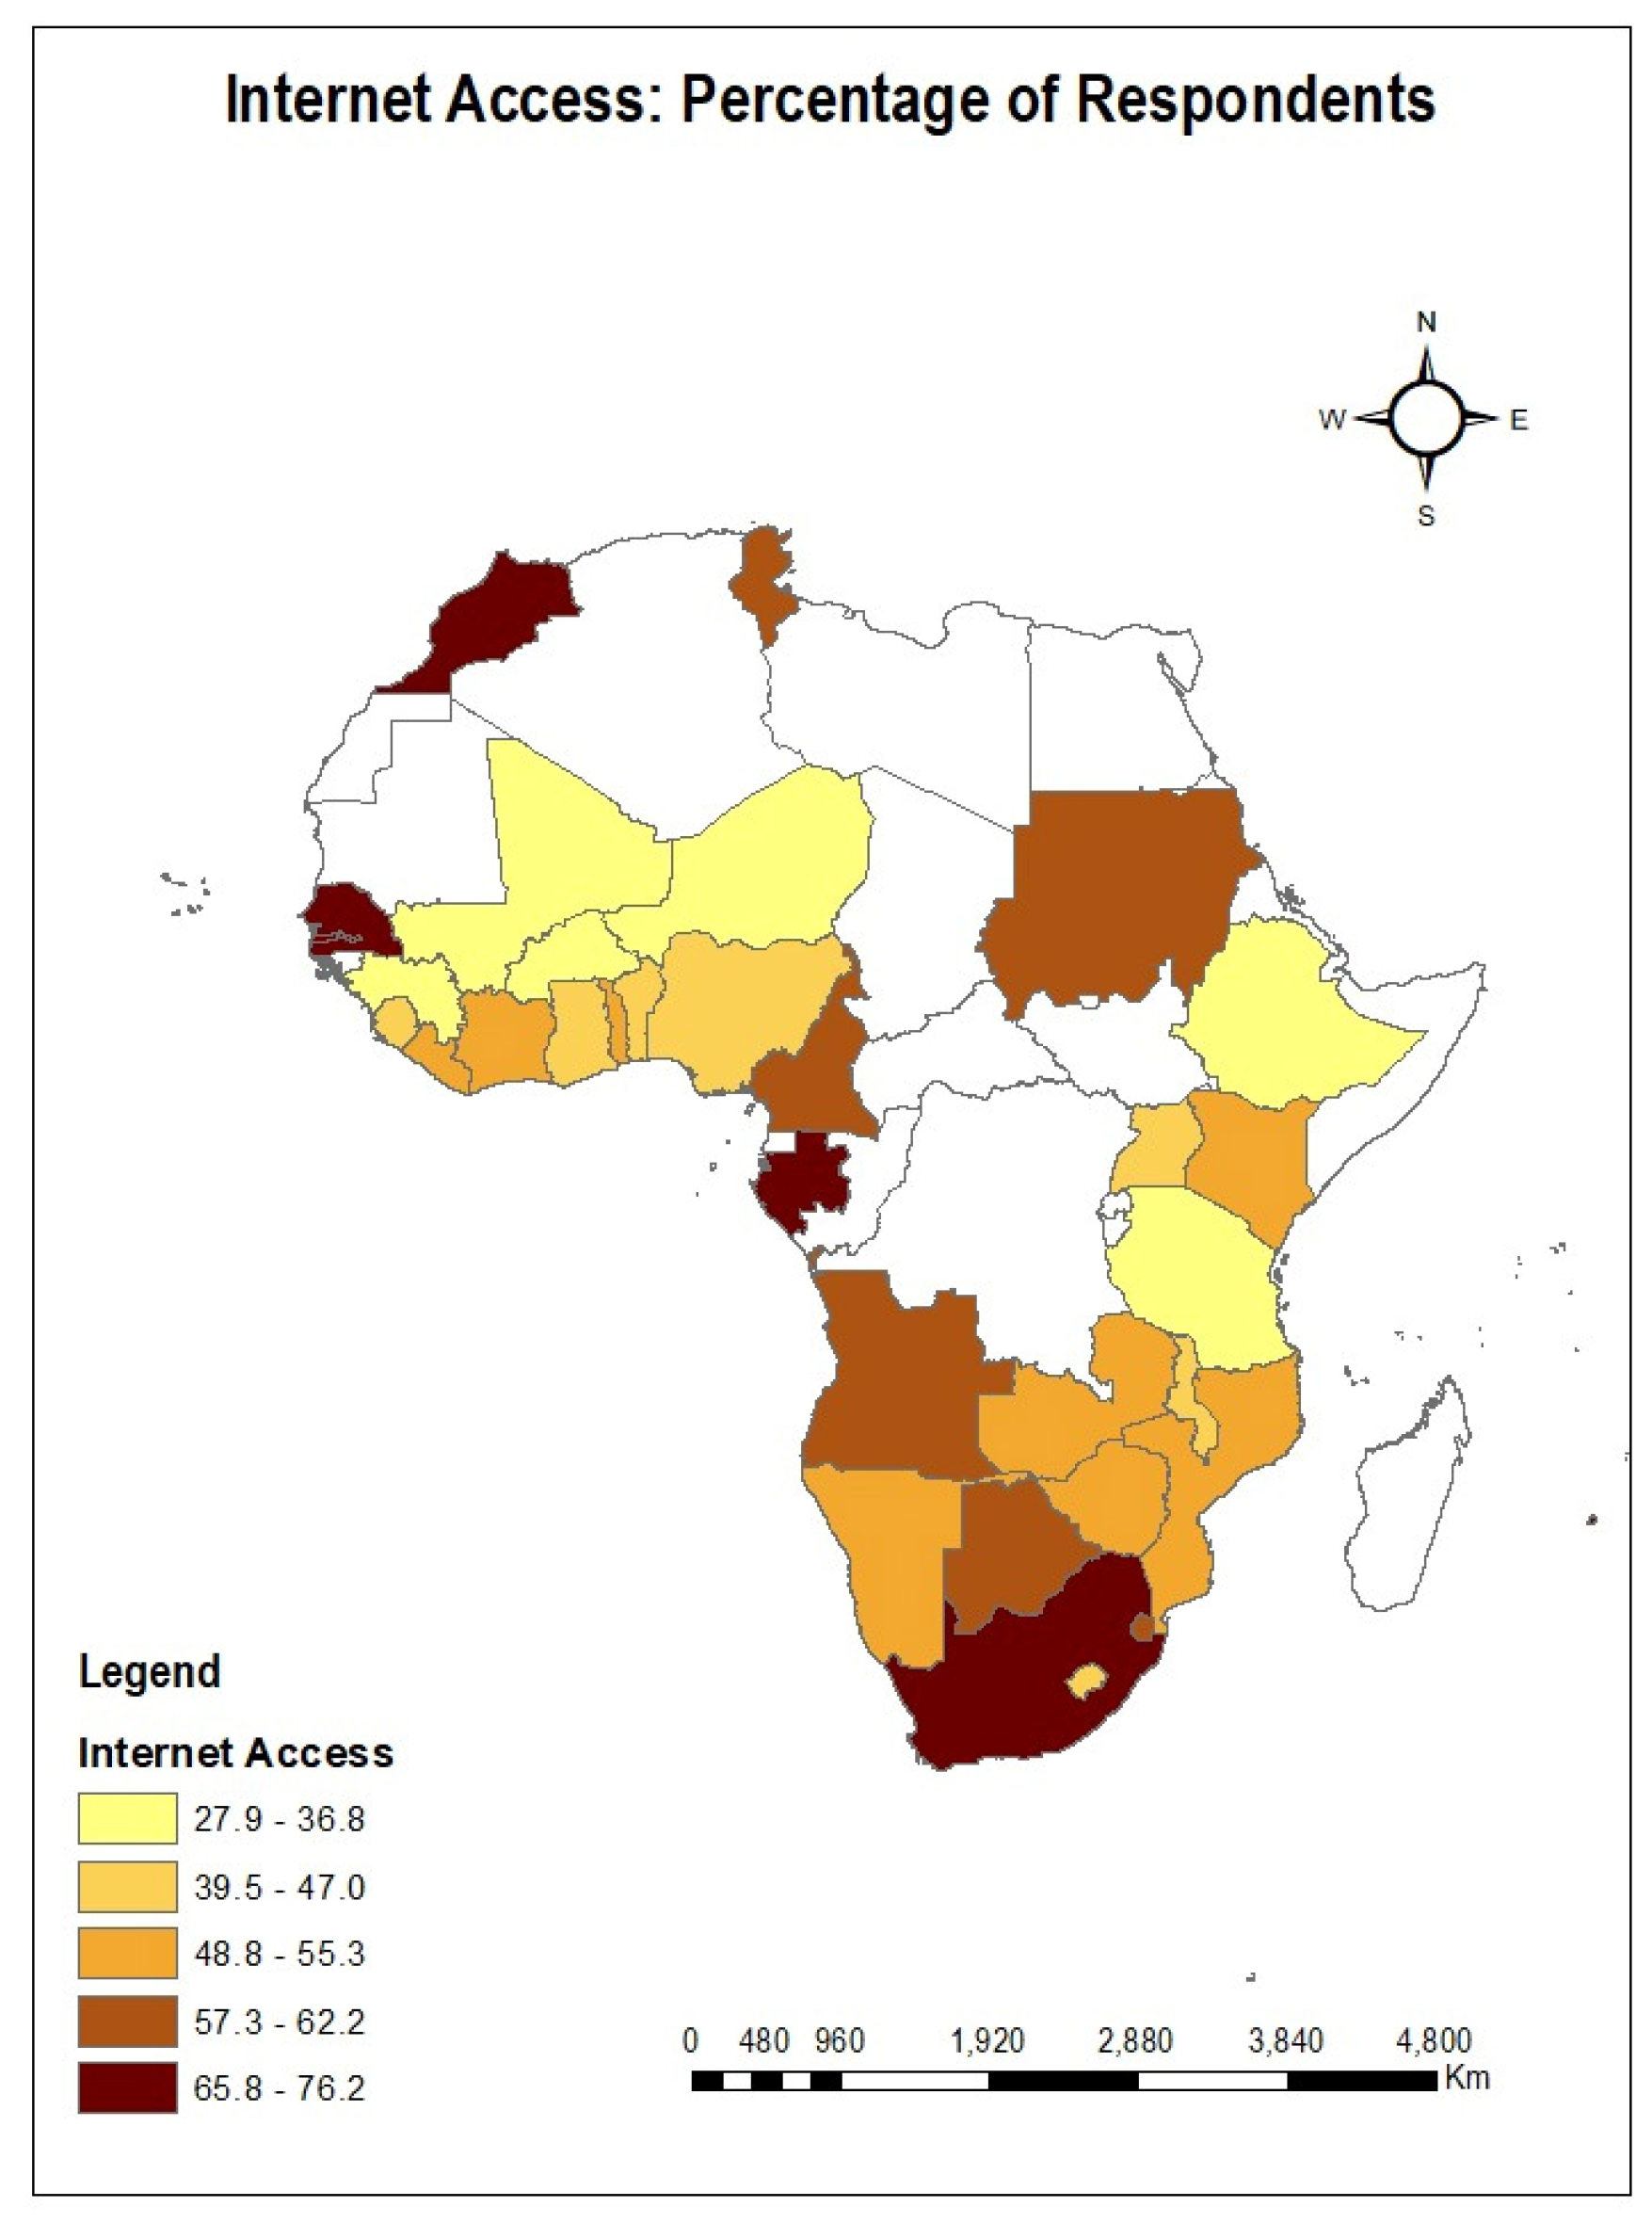
Figure 3.
Spatial distribution of Contact with a Health Facility across study countries.
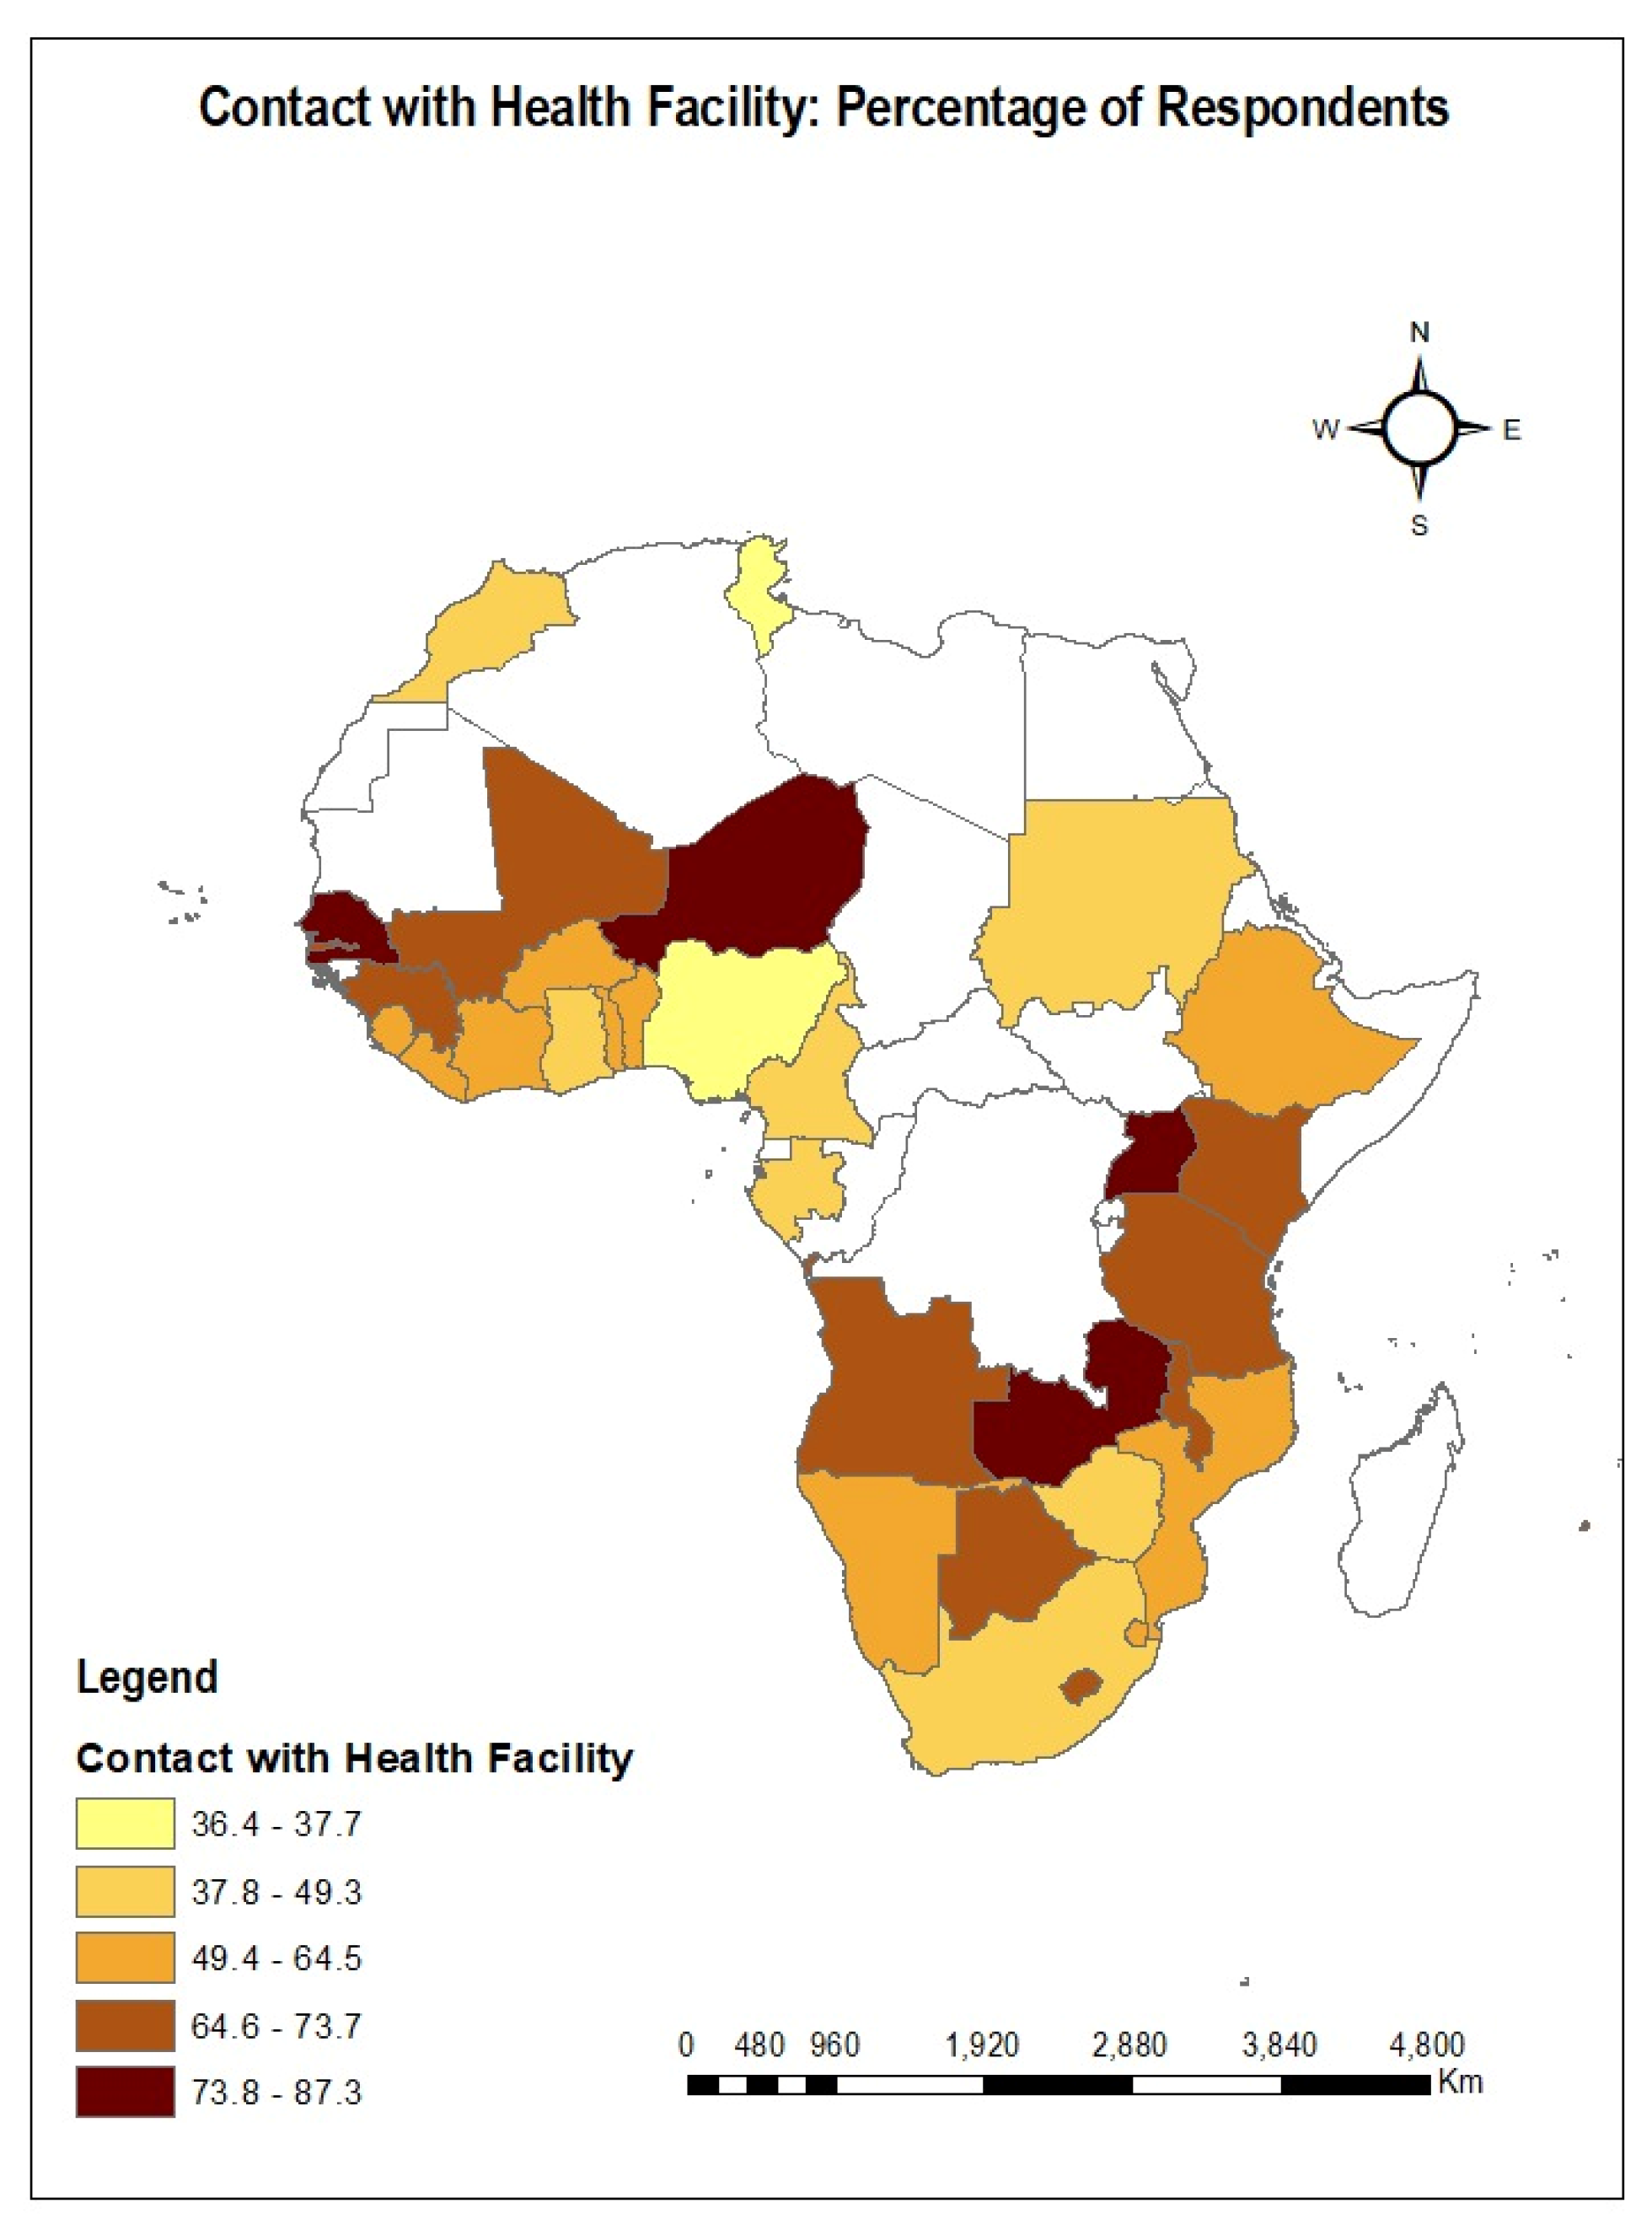
Figure 4.
Spatial distribution of lived poverty in across study countries (2022), stratified by quartile groupings of the Lived Poverty Index (LPI): lowest 25th percentile (left), 50th–75th percentile (middle), and highest 25th percentile (right).
Figure 4.
Spatial distribution of lived poverty in across study countries (2022), stratified by quartile groupings of the Lived Poverty Index (LPI): lowest 25th percentile (left), 50th–75th percentile (middle), and highest 25th percentile (right).
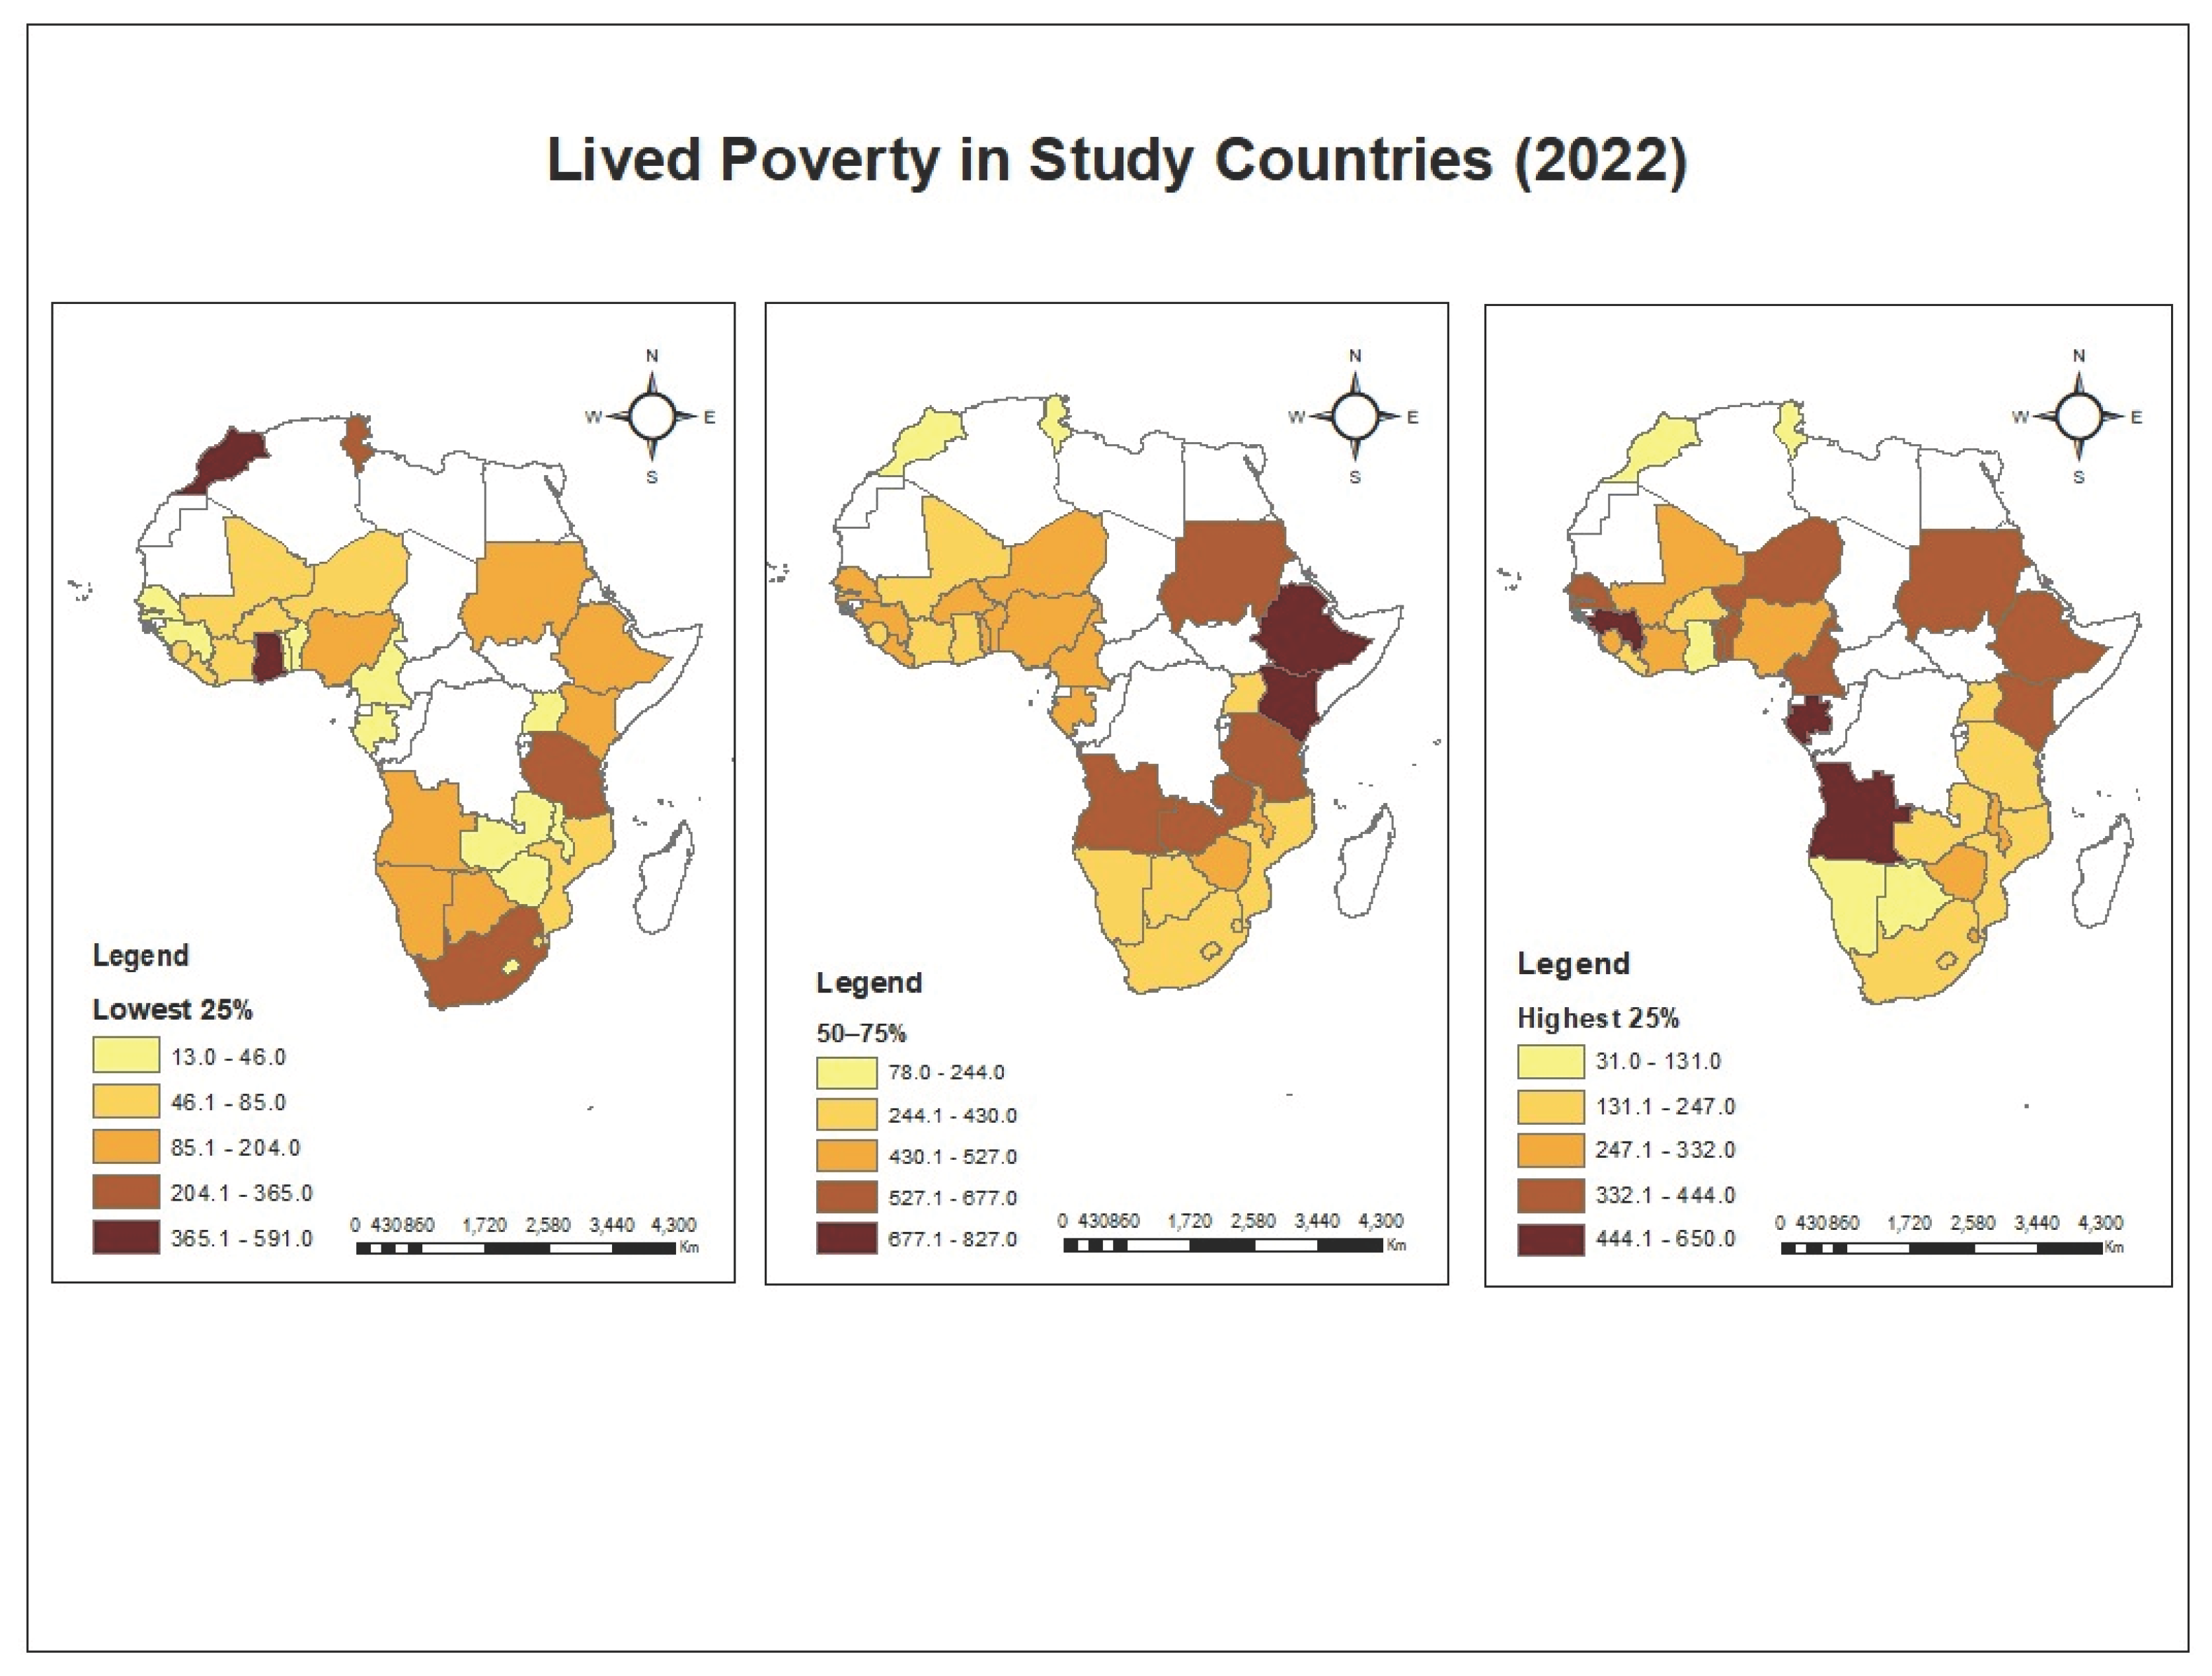

Table 1.
Sociodemographic characteristics, geographic characteristics, digital access and use, and healthcare contact among respondents (N=44,761).
Table 1.
Sociodemographic characteristics, geographic characteristics, digital access and use, and healthcare contact among respondents (N=44,761).
| Characteristic | Category | n (%) |
| Sociodemographic characteristics | ||
| Age group, years | 18–24 | 9,801 (21.9) |
| 25–34 | 13,119 (29.3) | |
| 35–44 | 9,410 (21.0) | |
| 45–54 | 6,089 (13.6) | |
| 55–64 | 3,707 (8.3) | |
| ≥65 | 2,635 (5.9) | |
| Sex | Male | 22,525 (50.3) |
| Female | 22,236 (49.7) | |
| Religion | Christian | 25,122 (56.1) |
| Muslim | 15,561 (34.8) | |
| Other | 4,078 (9.1) | |
| Educational attainment | No formal education | 8,596 (19.2) |
| Primary | 12,363 (27.6) | |
| Secondary | 16,096 (36.0) | |
| Post-secondary | 7,706 (17.2) | |
| Geographic characteristics | ||
| Place of residence | Urban/semi-urban | 20,516 (45.8) |
| Rural | 24,245 (54.2) | |
| African region | West Africa | 17,441 (39.0) |
| East Africa | 13,382 (29.9) | |
| North Africa | 3,965 (8.9) | |
| Southern Africa | 5,769 (12.9) | |
| Central Africa | 4,204 (9.4) | |
| Digital access and use | ||
| Mobile phone ownership | No household member owns a mobile phone | 4,023 (9.0) |
| Someone else in household owns a mobile phone | 3,323 (7.4) | |
| Personally owns a mobile phone | 37,415 (83.6) | |
| Frequency of mobile phone use | Never | 3,701 (8.3) |
| Less than once a month | 718 (1.6) | |
| A few times a month | 1,212 (2.7) | |
| A few times a week | 3,845 (8.6) | |
| Every day | 35,285 (78.8) | |
| Mobile phone internet access | No | 21,663 (48.4) |
| Yes | 23,098 (51.6) | |
| Frequency of obtaining news through social media | Never | 23,354 (52.2) |
| Less than once a month | 1,382 (3.1) | |
| A few times a month | 2,042 (4.6) | |
| A few times a week | 5,126 (11.5) | |
| Every day | 12,857 (28.7) | |
| Healthcare contact | ||
| Contact with a public clinic or hospital in the last 12 months | No | 17,396 (38.9) |
| Yes | 27,365 (61.1) |
Table 2.
Sequential logistic regression models examining relationships with contact with a public or private clinic.
Table 2.
Sequential logistic regression models examining relationships with contact with a public or private clinic.
| Predictor | Model 1: Phone ownership | Model 2: Model 1 + Frequency of phone use | Model 3: Model 2 + Phone access to internet | Model 4: Fully adjusted |
| Mobile phone ownership | ||||
| Overall P | .079 | .016 | .004 | .268 |
| Someone else in household owns a mobile phone | 1.053 (0.958–1.158), P=.286 | 1.018 (0.921–1.126), P=.722 | 1.025 (0.927–1.134), P=.626 | 1.089 (0.982–1.207), P=.105 |
| Personally owns a mobile phone | 0.971 (0.909–1.039), P=.395 | 0.898 (0.811–0.994), P=.037 | 0.886 (0.800–0.980), P=.019 | 1.054 (0.950–1.170), P=.321 |
| Frequency of phone use | ||||
| Overall P | — | .024 | .011 | <.001 |
| Less than once a month | — | 0.875 (0.743–1.030), P=.109 | 0.875 (0.743–1.031), P=.110 | 0.837 (0.709–0.988), P=.036 |
| A few times a month | — | 1.026 (0.893–1.178), P=.719 | 1.026 (0.893–1.178), P=.719 | 0.973 (0.845–1.120), P=.699 |
| A few times a week | — | 1.143 (1.021–1.278), P=.020 | 1.144 (1.022–1.280), P=.019 | 1.136 (1.013–1.273), P=.029 |
| Every day | — | 1.094 (0.983–1.216), P=.099 | 1.137 (1.021–1.265), P=.019 | 1.217 (1.091–1.357), P<.001 |
| Mobile phone internet access | ||||
| Yes | — | — | 0.850 (0.818–0.883), P<.001 | 1.081 (1.033–1.131), P=.001 |
| Age | — | — | — | |
| Overall P | — | — | — | <.001 |
| 25–34 | — | — | — | 1.257 (1.190–1.327), P<.001 |
| 35–44 | — | — | — | 1.281 (1.206–1.360), P<.001 |
| 45–54 | — | — | — | 1.289 (1.204–1.381), P<.001 |
| 55–64 | — | — | — | 1.359 (1.252–1.476), P<.001 |
| ≥65 | — | — | — | 1.577 (1.433–1.735), P<.001 |
| Gender | — | — | — | |
| Female | — | — | — | 1.338 (1.286–1.392), P<.001 |
| Education | — | — | — | |
| Overall P | — | — | — | <.001 |
| Primary | — | — | — | 1.071 (1.006–1.140), P=.033 |
| Secondary | — | — | — | 0.908 (0.851–0.969), P=.004 |
| Post-secondary | — | — | — | 0.808 (0.748–0.873), P<.001 |
| Religion | — | — | — | |
| Overall P | — | — | — | <.001 |
| Muslim | — | — | — | 1.257 (1.191–1.326), P<.001 |
| Other | — | — | — | 0.852 (0.796–0.912), P<.001 |
| Residence | — | — | — | |
| Rural | — | — | — | 1.143 (1.095–1.193), P<.001 |
| African region | — | — | — | |
| Overall P | — | — | — | <.001 |
| West Africa | — | — | — | Reference |
| Eastern Africa | — | — | — | 1.362 (1.293–1.435), P<.001 |
| Northern Africa | — | — | — | 0.411 (0.380–0.444), P<.001 |
| Southern Africa | — | — | — | 0.991 (0.927–1.059), P=.779 |
| Central Africa | — | — | — | 0.944 (0.877–1.016), P=.124 |
| Model fit | ||||
| −2 Log likelihood | 59,807.828 | 59,796.573 | 59,727.898 | 58,337.164 |
| Cox & Snell R² | .000 | .000 | .002 | .032 |
| Nagelkerke R² | .000 | .000 | .003 | .044 |
| Hosmer–Lemeshow χ² | 0.000 | 0.266 | 14.096 | 17.956 |
| Hosmer–Lemeshow df | 1 | 2 | 3 | 8 |
| Hosmer–Lemeshow P | 1.000 | .875 | .003 | .022 |
Notes: AORs are adjusted odds ratios with 95% CIs. *p < .05. Ref. = reference category. — = predictor not included in the model. ᵃ Model 4 additionally adjusts for age, sex, education, religion, residence, and African region. Outcome: self-reported contact with a public clinic or hospital (0 = no, 1 = yes).
Table 3.
Interaction analysis of mobile internet access and lived poverty in relation to healthcare-facility contact.
Table 3.
Interaction analysis of mobile internet access and lived poverty in relation to healthcare-facility contact.
| Predictor | AOR (95% CI) | p |
| Mobile phone internet access | ||
| No | Ref. | — |
| Yes | 1.074 (0.947–1.218) | .263 |
| Internet access × lived poverty | ||
| Internet access × low lived poverty | 1.043 (0.907–1.200) | .553 |
| Internet access × moderate lived poverty | 1.005 (0.873–1.157) | .943 |
| Internet access × high lived poverty | 1.021 (0.879–1.185) | .789 |
| Lived poverty | ||
| No lived poverty | Ref. | — |
| Low lived poverty | 1.418 (1.267–1.587) | <.001 |
| Moderate lived poverty | 1.709 (1.528–1.911) | <.001 |
| High lived poverty | 1.646 (1.466–1.849) | <.001 |
| Overall p | — | <.001 |
| Age group, years | ||
| 18–24 | Ref. | — |
| 25–34 | 1.261 (1.194–1.332) | <.001 |
| 35–44 | 1.292 (1.217–1.373) | <.001 |
| 45–54 | 1.320 (1.232–1.414) | <.001 |
| 55–64 | 1.400 (1.289–1.520) | <.001 |
| ≥65 | 1.617 (1.469–1.780) | <.001 |
| Overall p | — | <.001 |
| Sex | ||
| Male | Ref. | — |
| Female | 1.332 (1.281–1.386) | <.001 |
| Education | ||
| No formal education | Ref. | — |
| Primary | 1.125 (1.057–1.197) | <.001 |
| Secondary | 0.996 (0.935–1.061) | .911 |
| Post-secondary | 0.925 (0.857–0.997) | .042 |
| Overall p | — | <.001 |
| Religion | ||
| Christian | Ref. | — |
| Muslim | 1.253 (1.187–1.321) | <.001 |
| Other | 0.882 (0.823–0.944) | <.001 |
| Overall p | — | <.001 |
| Residence | ||
| Urban/semi-urban | Ref. | — |
| Rural | 1.075 (1.030–1.122) | .001 |
| African region | ||
| West Africa | Ref. | — |
| Eastern Africa | 1.351 (1.283–1.423) | <.001 |
| Northern Africa | 0.437 (0.404–0.472) | <.001 |
| Southern Africa | 0.993 (0.929–1.062) | .836 |
| Central Africa | 0.860 (0.798–0.926) | <.001 |
| Overall p | - | <.001 |
| Model fit | ||
| −2 log-likelihood | 58,142.267 | - |
| Cox & Snell R² | 0.037 | - |
| Nagelkerke R² | 0.050 | - |
| Hosmer–Lemeshow χ² (df) | 28.381 (8) | - |
| Hosmer–Lemeshow p | <.001 | - |
Notes: AORs are adjusted odds ratios with 95% CIs. Ref. = reference category. - = not applicable.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.