

Submitted:
27 September 2026
Posted:
29 September 2026
You are already at the latest version
Abstract
Background/Objectives: Osteoporosis and sarcopenia are associated with fractures, falls, and mortality. In prostate cancer, aging, advanced disease, and androgen deprivation therapy may accelerate concurrent bone and muscle loss. This study characterized longitudinal CT-derived musculoskeletal biomarkers in metastatic prostate cancer and evaluated the association between baseline osteosarcopenia and overall survival. Methods: This retrospective single-centre cohort included patients treated from 2009 to 2022, with follow-up imaging through 2024. An automated deep-learning pipeline quantified lumbar trabecular bone mineral density (BMD), psoas muscle volume (PV), psoas muscle density (PD), and volumetric psoas muscle index (vPMI). Osteosarcopenia was defined as concurrent osteoporosis (BMD < 135 HU) and sarcopenia (vPMI < 30). Survival from baseline CT was assessed using Kaplan-Meier analysis and multivariable Cox regression. Results: Among 437 patients with 3389 CT scans, osteoporosis, sarcopenia, and osteosarcopenia increased from 29.6%, 46.9%, and 17.2% at baseline to 54.0%, 82.8%, and 45.5% at final imaging. BMD declined by 2.1-3.7% annually, PD by 3.2-3.9%, and PV by 3.6-4.6% (all p < 0.0001). In the final year of life, PD declined by 12.0% and PV by 9.3%. Baseline osteosarcopenia remained independently associated with mortality after adjustment for age, time from diagnosis to baseline CT, PSA, and Gleason risk group (HR 2.11, 95% CI 1.50-2.99; p < 0.001). Conclusions: Osteosarcopenia is common and progressive in metastatic prostate cancer, and muscle loss accelerates near death. Baseline osteosarcopenia independently identifies patients at increased mortality risk. Automated analysis of routine surveillance CT may enable longitudinal musculoskeletal assessment and prognostic risk stratification.
Keywords:
aging
; artificial intelligence
; frailty
; prostate cancer
; osteosarcopenia
; sarcopenia
; osteoporosis
; musculoskeletal health
1. Introduction
In an aging population, osteopenia/osteoporosis (low bone mineral density) and sarcopenia (low muscle mass, quality, and strength) are growing public health concerns. In Canada, an estimated 2.3 million individuals are living with osteoporosis [1]. While it is challenging to identify sarcopenia prevalence due to variation in measurement techniques, estimates are between 9.9 – 40.4% of the population over 60 years old [2,3]. Elevated risks of fractures, falls, and mortality are associated with both osteoporosis and sarcopenia [4,5,6,7,8]. Osteosarcopenia represents the combination of these two pathologies, with the impact resulting in much higher risk of fracture than osteoporosis or sarcopenia alone [5,9].
Prostate cancer is the 4th most common cancer in Canada [10]. One in eight men will be affected and it is Canada’s 3rd leading cause of cancer death [11]. The incidence and prevalence of prostate cancer are increasing with our aging population. Unlike many malignancies, survival in prostate cancer is high, with 91% of patients diagnosed surviving at least 5 years [11]. The longevity of these patients is multi-factorial, but much can be attributed to androgen deprivation therapy (ADT) [12]. Osteosarcopenia is particularly relevant in prostate cancer, where patients are vulnerable to concurrent deterioration of bone and skeletal muscle due to aging, advanced disease, and treatment-related effects.
ADT is used for both metastatic and non-metastatic prostate cancer, with ~75% of prostate cancer patients receiving ADT treatment [12]. ADT works to limit prostate cancer progression by decreasing circulating androgens, primarily testosterone. Yet, testosterone is crucial for both bone and muscle maintenance in men [13]. The impacts of ADT on musculoskeletal health are significant [14,15], including an increase in fracture and falls risk over time [16,17,18]. In prostate cancer, the rate of osteoporosis is over 80% after > 10 years of ADT [19]; sarcopenia impacts over half of prostate cancer patients (56.6%; 21.8 – 87.4%) [2,3].
Clinically, imaging-based measures, such as dual energy x-ray absorptiometry (DEXA), are used to quantify bone mineral density (BMD) and identify individuals with osteopenia/osteoporosis [20,21]. However, little standardization exists of imaging-based techniques to diagnose sarcopenia; assessments are often focused on functional and clinical measures such as grip strength, and gait speed [22]. In recent years, interest has grown for developing imaging-based biomarkers to assess bone and muscle health through analysis of opportunistic computed tomography (CT) and magnetic resonance imaging (MRI) [20].
As individuals with prostate cancer live longer due to novel treatments [10,23], musculoskeletal health becomes an increasingly important factor in their quality of life. This study aimed to characterize longitudinal changes in bone and muscle health in patients with metastatic prostate cancer using imaging-based biomarkers derived from opportunistic cancer surveillance CT scans and to evaluate the association between baseline osteosarcopenia and overall survival.
2. Materials and Methods
2.1. Study Design
This large single-centre retrospective study evaluates temporal changes in osteosarcopenia imaging biomarkers in metastatic prostate cancer patients using opportunistic disease surveillance CT scans. Institutional ethics approval was obtained at Sunnybrook Health Sciences Centre (REB#1801).
2.2. Data Collection
The study utilized CT scans collected from Ontario Clinical Imaging Network (OCINet), on patients seen at the Odette Cancer Centre, Sunnybrook Health Sciences Centre, Toronto, Canada between January 1, 2009, and December 30, 2022. Follow-up imaging was captured until August 30, 2024.
- Inclusion criteria: patients with metastatic prostate cancer considered for systemic therapy between January 1, 2009, and December 30, 2022, with CT imaging including the lumbar spine.
- Exclusion criteria: no relevant CT imaging; non-metastatic prostate cancer; missing patient height for sarcopenia assessment.
Clinical data was captured from electronic medical health records until June 30, 2024, and compiled into a Research Electronic Data Capture (REDCap) database. Patient data collected included: standard demographic data (including height and weight), Gleason score/grade, prostate specific antigen results, tumor, nodes and metastasis staging, age at initial prostate cancer diagnosis, age at first available CT scan, and treatment information.
2.3. Automated Image Analysis Pipeline
CT scans involving the lumbar spine (DICOM format) were processed using an automated image analysis pipeline built using 3DSlicer, including custom Python-based analysis and deep-learning models [24,25]. Briefly, the pipeline identifies lumbar vertebrae (L1-L5) and their centroids and segments the vertebral bodies using a custom convolutional neural network (UNet) [26,27]. The segmented region is eroded to remove the cortical shell and enable measurement of the vertebral body trabecular bone mineral density (BMD). The psoas muscle is segmented using TotalSegmentator, an existing nnu-NET segmentation model [28]. The psoas segmentation is cropped to a consistent region using the L2/3 and L4/5 boundary planes, defined as perpendicular to the vector connecting the L2-L3 and L4-L5 vertebral body centroids. This ensures consistent scan-to-scan segmentation of the psoas muscle. Comparison of ground-truth manual segmentations of the psoas muscle with TotalSegmentator demonstrated a consistent under-segmentation of the psoas volume; therefore, a correction factor (x1.19) was applied to derive the true psoas volume. Based on the segmented regions of interest, the following biomarkers were calculated: average lumbar vertebral body trabecular BMD from L1 to L5 (mean and standard deviation), psoas muscle volume (PV) (of cropped region) and psoas muscle density (PD) (mean and standard deviation). Volumes were quantified in cm³ and densities in Hounsfield units (HU) [28].
2.4. Identification of Metastatic Involvement
Spinal metastatic lesions are common in prostate cancer. These lesions are typically osteoblastic and lead to hyperdense regions of bone. Given that, identification of radiographically involved metastatic vertebrae was required to identify changes in bone density reflective of local osteoblastic lesions vs. systemic bone health. To automate identification of non-metastatically involved vertebral levels, we developed a random forest classifier utilizing information from radiology reports (extracted with LLaMA 3.1 (8B)), BMD biomarkers, and a custom convolutional model trained to classify metastatically involved vertebrae. In an internal evaluation, this classifier was shown on a test set to have an accuracy of 85% and a negative predictive value of 93.3% on a held-out test set. Where questions remained regarding metastatic involvement, manual review of the imaging and radiology report were performed. Metastatically involved vertebrae were excluded from systemic BMD calculations.
2.5. Definitions: Osteoporosis, Sarcopenia, and Osteosarcopenia
Osteoporosis was defined as an average vertebral trabecular BMD < 135 HU, as established by Ahern et al., in metastasis-free vertebral bodies [29]. To define sarcopenia, we used a 3D volumetric psoas muscle index (vPMI), defined as PV (cm³) divided by height³ (m³). This 3D metric was found to have a strong correlation (r² = 0.91) to the existing 2D psoas muscle index [25]. Based on the 2D psoas muscle index threshold of < 6.35 cm²/m² for diagnosing sarcopenia, a vPMI < 30 was used as the threshold for sarcopenia [30]. Osteosarcopenia represents concurrence of osteoporosis and sarcopenia, reflecting patients with an average BMD < 135 HU and vPMI < 30.
2.6. Statistical Analysis
Statistical analysis was performed using R Studio (version 4.4.1). Continuous variables were summarized as medians with IQR unless noted. Categorical variables were reported as counts and percentages. Comparison of baseline demographic and patient subgroups was performed using analysis of variance (ANOVA) for continuous variables with normally distributed data and chi-square tests for categorical variables. When these tests were significant, post-hoc pairwise comparisons were performed with Bonferroni correction to identify specific group differences. For assessing longitudinal changes in biomarkers between first and last CT scans, paired T-tests were utilized. Annual percentage changes were calculated as total percentage change divided by follow-up duration in years.
To evaluate musculoskeletal changes prior to death, a reverse-time-to-death analysis was performed among deceased patients. Mean PD and PV were calculated for each of the 10 years preceding death. Linear regression models were fitted to estimate the yearly change in each variable, reflecting an annual rate of decline. A generalized additive model was used to explore the reverse-time-to-death analysis. This analysis was conducted at the population level to describe overall trends in muscle biomarkers prior to death. Overall survival was defined as the interval from first available CT scan to death from any cause. Patients alive at the end of clinical follow-up were censored at date of last known follow-up. Patients were classified to their baseline musculoskeletal phenotype using first available CT scan. Kaplan–Meier analysis was used to estimate overall survival of osteosarcopenia to the other cohorts combined using the log-rank test.
A multivariable Cox proportional hazards regression model was used to evaluate the association between baseline osteosarcopenia and all-cause mortality. Covariates included age at first CT, time with disease prior to first CT, log-transformed baseline PSA, and Gleason risk group. The proportional hazards assumption was assessed using Schoenfeld residuals. All statistical tests were two-sided and p < 0.05 was considered statistically significant.
3. Results
3.1. Study and Patient Characteristics
Overall, 437 patients with 3389 CT scans met inclusion criteria. Patient characteristics as classified by the total cohort and 4 baseline musculoskeletal phenotype are summarized in Table 1. Mortality status was known for 426/437 (97.5%) of patients with 328/437 (75.1%) deceased, with no difference of distribution (deceased, alive, unknown) between 4 baseline groups. Average age at diagnosis was 66.7yrs (61.0-72.5). The osteosarcopenia cohort (71.8yrs; 66.3-76.6) was older at diagnosis than the overall cohort (p <0.001), had lived longer with prostate cancer (p = 0.004) before 1st CT scan, and were significantly older at time of death (p < 0.001). Interestingly, there was a greater proportion of low-risk Gleason risk group patients in the osteosarcopenia cohort (13/75 patients; 17.3%) than in the other cohorts (p = 0.045). PSA at time of diagnosis was similar between groups (p = 0.21).
3.2. Bone Density
Osteoporosis prevalence increased from 29.6% (127/437) at baseline to 54.0% (236/437) at the final CT scan. Over the study, patients with baseline osteosarcopenia lost 2.1% of their BMD per year (average total loss = 6.4%). In comparison, the other groups had more drastic BMD decreases (14.9-18.8%; p < 0.0001). Specifically, those with no osteoporosis or sarcopenia (NOS) lost 3.7% of their BMD/yr and 18.8% of their baseline BMD. The yearly BMD changes are similar for the sarcopenic and osteoporotic groups (-3.5% and -3.4%, annually). The absolute change was -14.9% for the sarcopenic cohort and -15.2% for the osteoporotic. All groups experienced significant decreases in BMD over follow-up (osteosarcopenia cohort <0.05, all others p < 0.0001). (Table 2B).
3.3. Psoas Muscle Density
PD decreased in all sub-groups (-3.2% to -3.9%/yr, p < 0.0001). The total change in PD ranged from -13.6% in the osteosarcopenic cohort to -21.2% in the NOS cohort; the PD of the osteoporotic and sarcopenic groups decreased 17.4% and 19.3%, respectively (Table 2C).
3.4. Corrected Psoas Volume
All phenotypes experienced large PV decreases in follow-up (p < 0.0001 for all groups). The PV changes ranged from -26.9% to -14.5% (-4.6% to -3.6%/yr) with the largest decreases in the NOS cohort (Table 2A).
3.5. Sarcopenia Assessment
Volumetric psoas muscle index (vPMI) decrease ranged from -5.3%/yr in the NOS group to -4.3%/yr in the sarcopenic group (p < 0.0001 for all). The sarcopenia and osteosarcopenia cohorts were far below the vPMI sarcopenia threshold, even at baseline. The NOS and osteoporotic groups fell below the threshold at the last CT (vPMI decreased from 36.8 to 26.8 and 35.3 to 28.1, respectively; Table 2D).
3.6. Psoas Muscle Density and Corrected Psoas Volume Changes during the Terminal Phase of Prostate Cancer
In patients that died, a reverse time analysis evaluated changes in muscle nearing death. The rate of PD and PV decrease was drastically faster in the last year of life. PD change was ~-1% per year until 3 years before death, -2.07% and -4.65% in the third and second years before death, and -12.00% in the final year of life (Figure 1A). PV followed a similar trajectory from ~-1% to -9.32% in the year preceding death (Figure 1B).
3.7. Baseline Musculoskeletal Phenotype and Overall Survival
Baseline musculoskeletal phenotype was associated with overall survival (Figure 2). Kaplan–Meier survival estimates demonstrated early and clear separation between osteosarcopenia and the other cohorts, with baseline osteosarcopenia being associated with poorest survival. Survival trajectories were similar between non-osteosarcopenia cohorts. Patients with osteosarcopenia at baseline experienced significantly worse overall survival compared to patients without osteosarcopenia (log-rank χ² = 30.56, df = 1, p < 0.001).
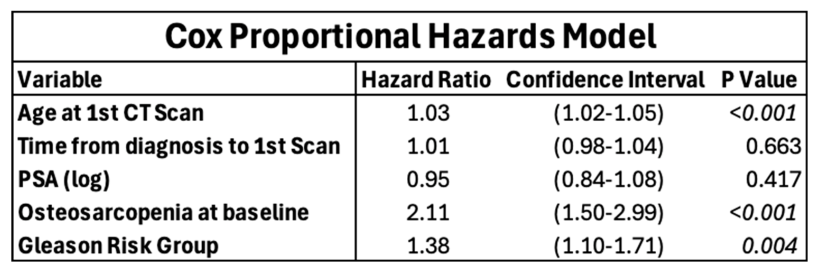
In multivariable Cox analysis, baseline osteosarcopenia remained independently associated with increased mortality after adjustment for age at 1st CT, time from diagnosis to 1st CT, PSA at diagnosis (log), and Gleason risk group (HR 2.11, 95% CI 1.50-2.99; p < 0.001) (Table 3). Gleason risk group (HR 1.38, 95% CI 1.10-1.71; p = 0.004) and advanced age (HR 1.03/year, 95% CI 1.02-1.05; p < 0.001) were also associated with mortality. Time from diagnosis to first CT and baseline PSA were not independently associated with mortality.
4. Discussion
In prostate cancer, disease surveillance CT scans represent an opportunity to quantify bone and muscle health and identify osteosarcopenia without additional cost to the patient or healthcare system [6,21,31,32]. Through longitudinal evaluation of 3D CT-based biomarkers, we show that osteosarcopenia is highly prevalent and progressive in metastatic prostate cancer, accelerates as patients approach death, and is associated with overall survival. Importantly, osteosarcopenia identified on first available CT scan was independently associated with overall survival.
Declines in bone and muscle health are known to occur in aging. Bleicher et al. showed that BMD in men decreases 0.4% annually between ages 70-75, and by 1.2% per year in men >85yrs [33]. Cawthon et al. reported that BMD decreased 2.9% over 4.6 years in men >65yrs (-0.63%/yr) with the rate increasing with age [34]. BMD loss in our cohort was much greater (-2.1% to -3.7%), reinforcing that patients with advanced prostate cancer experience a disproportionate decrease in BMD and at a younger age.
It is estimated that 3.1-5.6% of community dwelling adults and 18.9-33.1% of elderly populations are sarcopenic [35]. These estimates are lower than our observed sarcopenia rate (46.9%) at first imaging, suggesting an impact of prostate cancer and/or its treatment on muscle health. This mirrors results from Kovač et al., who reported sarcopenia in 43.8% of patients across 24 prostate cancer studies [3]. Surov and Wienke reviewed the prevalence of sarcopenia in patients with solid tumours from 280 studies (81,814 patients), estimating sarcopenia prevalence of 48.5%-55.4% in early prostate cancer and 72.2-79.9% in palliative settings [2]. The latter aligns with sarcopenia prevalence of 82.8% at the final scan in our analysis.
The association between osteosarcopenia and mortality represents an important finding of this study. Patients with osteosarcopenia demonstrated poorest overall survival and osteosarcopenia was associated with a 2.11 HR in comparison to those without osteosarcopenia. Similarly, Wang et al. highlight the impact of osteosarcopenia on survival in cancer patients [4], where individuals with osteosarcopenia had worse disease-free survival (HR 2.17; 1.62-2.92). The independent association between osteosarcopenia and mortality further suggests that the observed survival difference is not solely explained by older age or other markers of prostate cancer severity.
This study found a drastic acceleration of PD and PV decreases as patients approached death, similar to other reports of accelerated muscle loss prior to death in cancer patients [36,37]. Babic et al, showed that pancreatic cancer patients experiencing the greatest muscle loss had decreased survival [38]. We found relatively stable decreases in PD and PV until the last two years before death; such changes may represent a quantifiable physical deterioration that may present prognostic benefit prior to current clinical indicators. These findings suggest that baseline musculoskeletal phenotype may provide some prognostic information, while longitudinal biomarker trajectories may inform evolving physiological deterioration.
The automated nature of the imaging pipeline is particularly useful in diseases such as prostate cancer where routine disease surveillance imaging is performed. Conventional assessment of osteoporosis and sarcopenia requires dedicated investigations that are inconsistently performed. In contrast, opportunistic analysis of surveillance CT scans allows for repeated assessment of musculoskeletal health without added demand of the patient or the healthcare system.
This study has several limitations. Its retrospective single-centre design limits causal inference. Skeletal metastasis limited vertebral levels available for BMD calculations in some patients. The imaging-based definition of sarcopenia lacks clinical correlates such grip strength or gait speed. Although baseline osteosarcopenia was independently associated with mortality, residual confounding from variable types and duration of treatments used in individual patients, metastatic burden, and comorbidities remains possible. Prospective studies integrating serial CT-derived biomarkers with treatment, functional, and disease-specific variables are required to determine the clinical and prognostic utility of these measures.
5. Conclusions
Musculoskeletal deterioration is highly prevalent and progressive in metastatic prostate cancer. Osteosarcopenia prevalence increased substantially, while muscle density and volume declined rapidly as patients approached death. Osteosarcopenia was independently associated with more than twice the hazard ratio of mortality, suggesting that concurrent bone and muscle deterioration may identify a clinically vulnerable population. Automated extraction of musculoskeletal biomarkers from routine cancer surveillance CT imaging provides a scalable approach for longitudinal assessment and may offer clinically relevant prognostic information without additional imaging or patient burden.
Author Contributions
Conceptualization, T.D.R., U.E. and M.H.; methodology, T.D.R., C.W. and M.H.; software, S.T. and M.H.; formal analysis, T.D.R. and M.H.; investigation, R.Y. and M.H.; data curation, T.D.R., S.T. and M.H.; writing—original draft preparation, T.D.R., R.Y., U.E., C.W. and M.H.; writing—review and editing, T.D.R., R.Y., U.E., C.W. and M.H.; supervision, U.E., C.W. and M.H.; funding acquisition, C.W. and M.H. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by the Canadian Institutes of Health Research (grant #452060), the Hold’em for Life Charity, the Surgeon Scientist Training Program at the University of Toronto, the SCACE Graduate Fellowship in Prostate Cancer Research, and the Comprehensive Research Experience for Medical Students Summer Research Program.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board (or Ethics Committee) of Sunnybrook Health Sciences Centre (REB#1801 – June 13, 2025).
Informed Consent Statement
Not applicable.
Data Availability Statement
The data presented in this study are available from the corresponding author upon reasonable request. The data are not publicly available due to patient privacy and ethical restrictions.
Acknowledgments
The authors would like to thank Dr. Normand Robert for assistance in imaging data acquisition.
Conflicts of Interest
The authors declare no conflicts of interest. The funders had no role in the design of the study; in the collection, analysis, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Abbreviations
The following abbreviations are used in this manuscript:
| ADT | Androgen deprivation therapy |
| ANOVA | Analysis of variance |
| BMD | Bone mineral density |
| CI | Confidence interval |
| CT | Computed tomography |
| DEXA | Dual-energy X-ray absorptiometry |
| DICOM | Digital Imaging and Communications in Medicine |
| HR | Hazard ratio |
| HU | Hounsfield units |
| IQR | Interquartile range |
| MRI | Magnetic resonance imaging |
| NOS | No osteoporosis or sarcopenia |
| OCINet | Ontario Clinical Imaging Network |
| PD | Psoas muscle density |
| PSA | Prostate-specific antigen |
| PV | Psoas muscle volume |
| REB | Research Ethics Board |
| REDCap | Research Electronic Data Capture |
| vPMI | Volumetric psoas muscle index |
References
- Osteoporosis Canada. 2022 Osteoporosis Canada Facts and Stats. Available online: https://osteoporosis.ca/wp-content/uploads/2022-Osteoporosis-Canada-Facts-and-Stats_Web.pdf#page=1.42 (accessed on 19 May 2025).
- Surov, A.; Wienke, A. Prevalence of sarcopenia in patients with solid tumors: A meta-analysis based on 81,814 patients. JPEN J. Parenter. Enter. Nutr. 2022, 46(8), 1761–1768. [Google Scholar] [CrossRef]
- Kovac, M.B.; Pavlin, T.; Cavka, L.; et al. The trajectory of sarcopenia following diagnosis of prostate cancer: A systematic review and meta-analysis. J. Geriatr. Oncol. 2023, 14(7), 101594. [Google Scholar] [CrossRef]
- Wang, C.C.; Liu, H.C.; Lin, W.L.; et al. Osteosarcopenia in patients with cancer: A systematic review and meta-analysis. Medicine 2024, 103(45), e40476. [Google Scholar] [CrossRef]
- Paulin, T.K.; Malmgren, L.; McGuigan, F.E.; Akesson, K.E. Osteosarcopenia: Prevalence and 10-Year Fracture and Mortality Risk—A Longitudinal, Population-Based Study of 75-Year-Old Women. In Calcif Tissue Int.; 2024. [Google Scholar] [CrossRef]
- Solla-Suarez, P.; Arif, S.G.; Ahmad, F.; et al. Osteosarcopenia and Mortality in Older Adults Undergoing Transcatheter Aortic Valve Replacement. JAMA Cardiol. 2024, 9(7), 611–618. [Google Scholar] [CrossRef]
- Chen, S.; Xu, X.; Gong, H.; et al. Global epidemiological features and impact of osteosarcopenia: A comprehensive meta-analysis and systematic review. J. Cachexia Sarcopenia Muscle 2024, 15(1), 8–20. [Google Scholar] [CrossRef]
- Lee, A.; McArthur, C.; Ioannidis, G.; et al. Associations between Osteosarcopenia and Falls, Fractures, and Frailty in Older Adults: Results From the Canadian Longitudinal Study on Aging (CLSA). J. Am. Med. Dir. Assoc. 2024, 25(1), 167–176.e6. [Google Scholar] [CrossRef]
- Huo, Y.R.; Suriyaarachchi, P.; Gomez, F.; et al. Phenotype of osteosarcopenia in older individuals with a history of falling. J. Am. Med. Dir. Assoc. 2015, 16(4), 290–295. [Google Scholar] [CrossRef]
- Canadian Cancer Society. Prostate Cancer Statistics. 2023.
- Ellison, L.F.; Saint-Jacques, N. Five-year cancer survival by stage at diagnosis in Canada. Health Rep. 2023, 34(1), 3–15. [Google Scholar] [CrossRef]
- Borno, H.T.; Lichtensztajn, D.Y.; Gomez, S.L.; Palmer, N.R.; Ryan, C.J. Differential use of medical versus surgical androgen deprivation therapy for patients with metastatic prostate cancer. Cancer 2019, 125(3), 453–462. [Google Scholar] [CrossRef]
- Rojas-Zambrano, J.G.; Rojas-Zambrano, A.; Rojas-Zambrano, A.F. Impact of Testosterone on Male Health: A Systematic Review. Cureus 2025, 17(4), e82917. [Google Scholar] [CrossRef]
- Blow, T.A.; Murthy, A.; Grover, R.; et al. Profiling of Skeletal Muscle and Adipose Tissue Depots in Men with Advanced Prostate Cancer Receiving Different Forms of Androgen Deprivation Therapy. Eur. Urol. Open Sci. 2023, 57, 1–7. [Google Scholar] [CrossRef]
- Papadopoulos, E.; Wong, A.K.O.; Law, S.H.C.; et al. The impact of sarcopenia on clinical outcomes in men with metastatic castrate-resistant prostate cancer. PLoS ONE 2023, 18(6), e0286381. [Google Scholar] [CrossRef]
- Mazziotti, G.; Lania, A.G.; Lagana, M.; Berruti, A. Prediction of fragility fractures in men with prostate cancer under androgen deprivation therapy: the importance of a multidisciplinary approach using a mini-invasive diagnostic tool. Endocrine 2023. [Google Scholar] [CrossRef]
- Stelmach-Mardas, M.; Warchol, W.; Garczyk, A.; et al. Influence of Androgen Deprivation Therapy on the Development of Sarcopenia in Patients with Prostate Cancer: A Systematic Review. Nutrients 2024, 16(5), 656. [Google Scholar] [CrossRef]
- Rier, H.N.; Jager, A.; Sleijfer, S.; Maier, A.B.; Levin, M.D. The Prevalence and Prognostic Value of Low Muscle Mass in Cancer Patients: A Review of the Literature. Oncologist 2016, 21(11), 1396–1409. [Google Scholar] [CrossRef]
- Morote, J.; Morin, J.P.; Orsola, A.; et al. Prevalence of osteoporosis during long-term androgen deprivation therapy in patients with prostate cancer. Urology 2007, 69(3), 500–504. [Google Scholar] [CrossRef]
- Deshpande, N.; Hadi, M.S.; Lillard, J.C.; et al. Alternatives to DEXA for the assessment of bone density: a systematic review of the literature and future recommendations. J. Neurosurg. Spine 2023, 38(4), 436–445. [Google Scholar] [CrossRef]
- Sangondimath, G.; Sen, R.K.; T, F.R. DEXA and Imaging in Osteoporosis. Indian J. Orthop. 2023, 57 (Suppl 1), 82–93. [Google Scholar] [CrossRef]
- Cruz-Jentoft, A.J.; Bahat, G.; Bauer, J.; et al. Sarcopenia: revised European consensus on definition and diagnosis. Age Ageing 2019, 48(1), 16–31. [Google Scholar] [CrossRef]
- Alyamani, N.; Song, J.; van Katwyk, S.; et al. Cost-Utility Analysis of Radiation Treatment Modalities for Intermediate-Risk Prostate Cancer. Curr. Oncol. 2021, 28(4), 2385–2398. [Google Scholar] [CrossRef]
- Tabatabaei, S.; Ross, T.D.; Emmenegger, U.; Whyne, C.M.; Hardisty, M. Quantification of 3D Musculoskeletal CT Image-Based Biomarkers in the Lumbar Spine: Application in Metastatic Prostate Cancer. In Medical Image Computing and Computer Assisted Intervention—MICCAI 2026; Yang, G., et al., Eds.; Lecture Notes in Computer Science; Springer: Cham, Switzerland, 2027; Volume 16885, pp. 532–542. [Google Scholar] [CrossRef]
- Castano Sainz, Y.; Chen, S.Y.; Tabatabaei, S.; Ross, T.D.; Whyne, C.M.; Detsky, J.; Sahgal, A.; Hardisty, M.R. Characterization of osteosarcopenia in spinal metastases patients to be treated with stereotactic body radiotherapy using quantitative image-based AI-derived biomarkers. In Proceedings of the 12th International Conference on Bioinformatics Research and Applications (ICBRA 2025), Prague, Czech Republic, 22 December 2025; Association for Computing Machinery: New York, NY, USA; 2025, pp. 27–32. [Google Scholar] [CrossRef]
- Klein, G.; Hardisty, M.; Whyne, C.M.; Martel, A.L. VertDetect: Fully End-to-End 3D Vertebral Instance Segmentation Model. arXiv 2023, arXiv:2311.09958. [Google Scholar] [CrossRef]
- Klein, G.; Martel, A.L.; Sahgal, A.; Whyne, C.; Hardisty, M. Metastatic Vertebrae Segmentation for Use in a Clinical Pipeline. In Computational Methods and Clinical Applications for Spine Imaging; Springer: Cham, Switzerland, 2020; Volume 11963, pp. 15–28. [Google Scholar] [CrossRef]
- Wasserthal, J.; Breit, H.C.; Meyer, M.T.; et al. TotalSegmentator: Robust Segmentation of 104 Anatomic Structures in CT Images. Radiol. Artif. Intell. 2023, 5(5), e230024. [Google Scholar] [CrossRef]
- Ahern, D.P.; McDonnell, J.; Riffault, M.; et al. A Meta-Analysis of the Diagnostic Accuracy of Hounsfield Units on Computed Topography Relative to Dual-Energy X-ray Absorptiometry for the Diagnosis of Osteoporosis in the Spine Surgery Population. Spine J. 2021. [Google Scholar] [CrossRef]
- Manabe, T.; Ogawa, C.; Takuma, K.; et al. Usefulness of the Measurement of Psoas Muscle Volume for Sarcopenia Diagnosis in Patients with Liver Disease. Diagnostics 2023, 13(7), 1245. [Google Scholar] [CrossRef]
- Praveen, A.D.; Sollmann, N.; Baum, T.; Ferguson, S.J.; Benedikt, H. CT image-based biomarkers for opportunistic screening of osteoporotic fractures: a systematic review and meta-analysis. Osteoporos Int. 2024. [Google Scholar] [CrossRef]
- Voulgaridou, G.; Tyrovolas, S.; Detopoulou, P.; et al. Diagnostic Criteria and Measurement Techniques of Sarcopenia: A Critical Evaluation of the Up-to-Date Evidence. Nutrients 2024, 16(3), 436. [Google Scholar] [CrossRef]
- Bleicher, K.; Cumming, R.G.; Naganathan, V.; et al. Predictors of the rate of BMD loss in older men: findings from the CHAMP study. Osteoporos. Int. 2013, 24(7), 1951–1963. [Google Scholar] [CrossRef]
- Cawthon, P.M.; Ewing, S.K.; McCulloch, C.E.; et al. Loss of hip BMD in older men: the osteoporotic fractures in men (MrOS) study. J. Bone Min. Res. 2009, 24(10), 1728–1735. [Google Scholar] [CrossRef]
- Westbury, L.D.; Beaudart, C.; Bruyere, O.; et al. Recent sarcopenia definitions—prevalence, agreement and mortality associations among men: Findings from population-based cohorts. J. Cachexia Sarcopenia Muscle 2023, 14(1), 565–575. [Google Scholar] [CrossRef]
- Kubo, Y.; Naito, T.; Mori, K.; Osawa, G.; Aruga, E. Skeletal muscle loss and prognosis of breast cancer patients. Support Care Cancer 2017, 25(7), 2221–2227. [Google Scholar] [CrossRef]
- Wallengren, O.; Iresjo, B.M.; Lundholm, K.; Bosaeus, I. Loss of muscle mass in the end of life in patients with advanced cancer. Support Care Cancer 2015, 23(1), 79–86. [Google Scholar] [CrossRef]
- Babic, A.; Rosenthal, M.H.; Bamlet, W.R.; et al. Postdiagnosis Loss of Skeletal Muscle, but Not Adipose Tissue, Is Associated with Shorter Survival of Patients with Advanced Pancreatic Cancer. Cancer Epidemiol. Biomark. Prev. 2019, 28(12), 2062–2069. [Google Scholar] [CrossRef]
Figure 1.
Trajectories of psoas muscle density (A) and psoas muscle volume (B) in the last 5 years of life. Years −10 to −3 reflected relatively consistent decreases in psoas muscle density (range −1.48% to 0.09% per year) and corrected psoas muscle volume (range −2.19% to −0.58% per year). Blue line represents the generalized additive model with 95% confidence interval represented by shaded area.
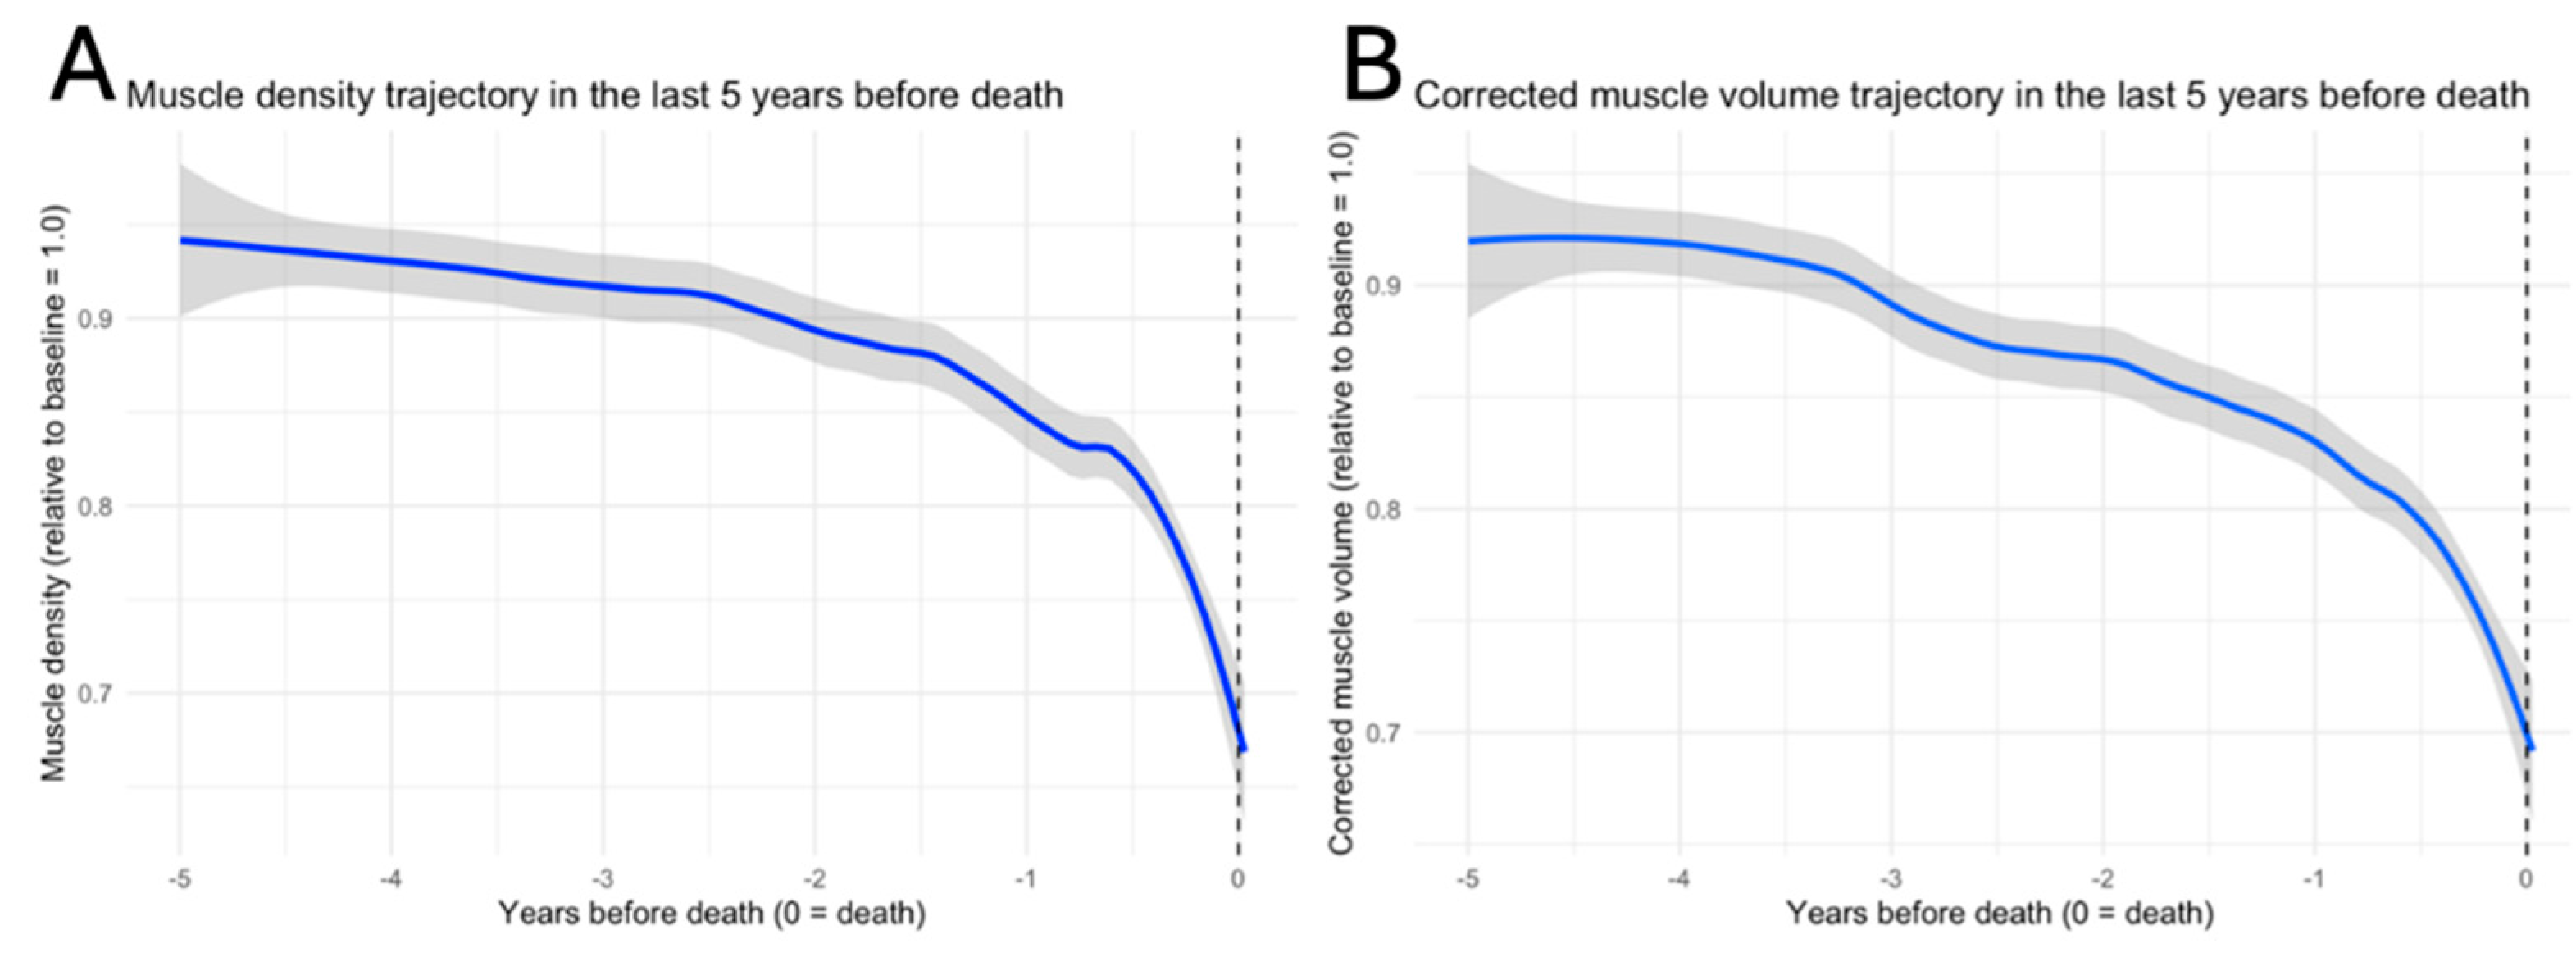
Figure 2.
Kaplan–Meier estimates of overall survival according to baseline osteosarcopenia status. Baseline was defined as the first available CT examination. Patients with osteosarcopenia were compared with the reference group comprising patients without osteosarcopenia.
Figure 2.
Kaplan–Meier estimates of overall survival according to baseline osteosarcopenia status. Baseline was defined as the first available CT examination. Patients with osteosarcopenia were compared with the reference group comprising patients without osteosarcopenia.
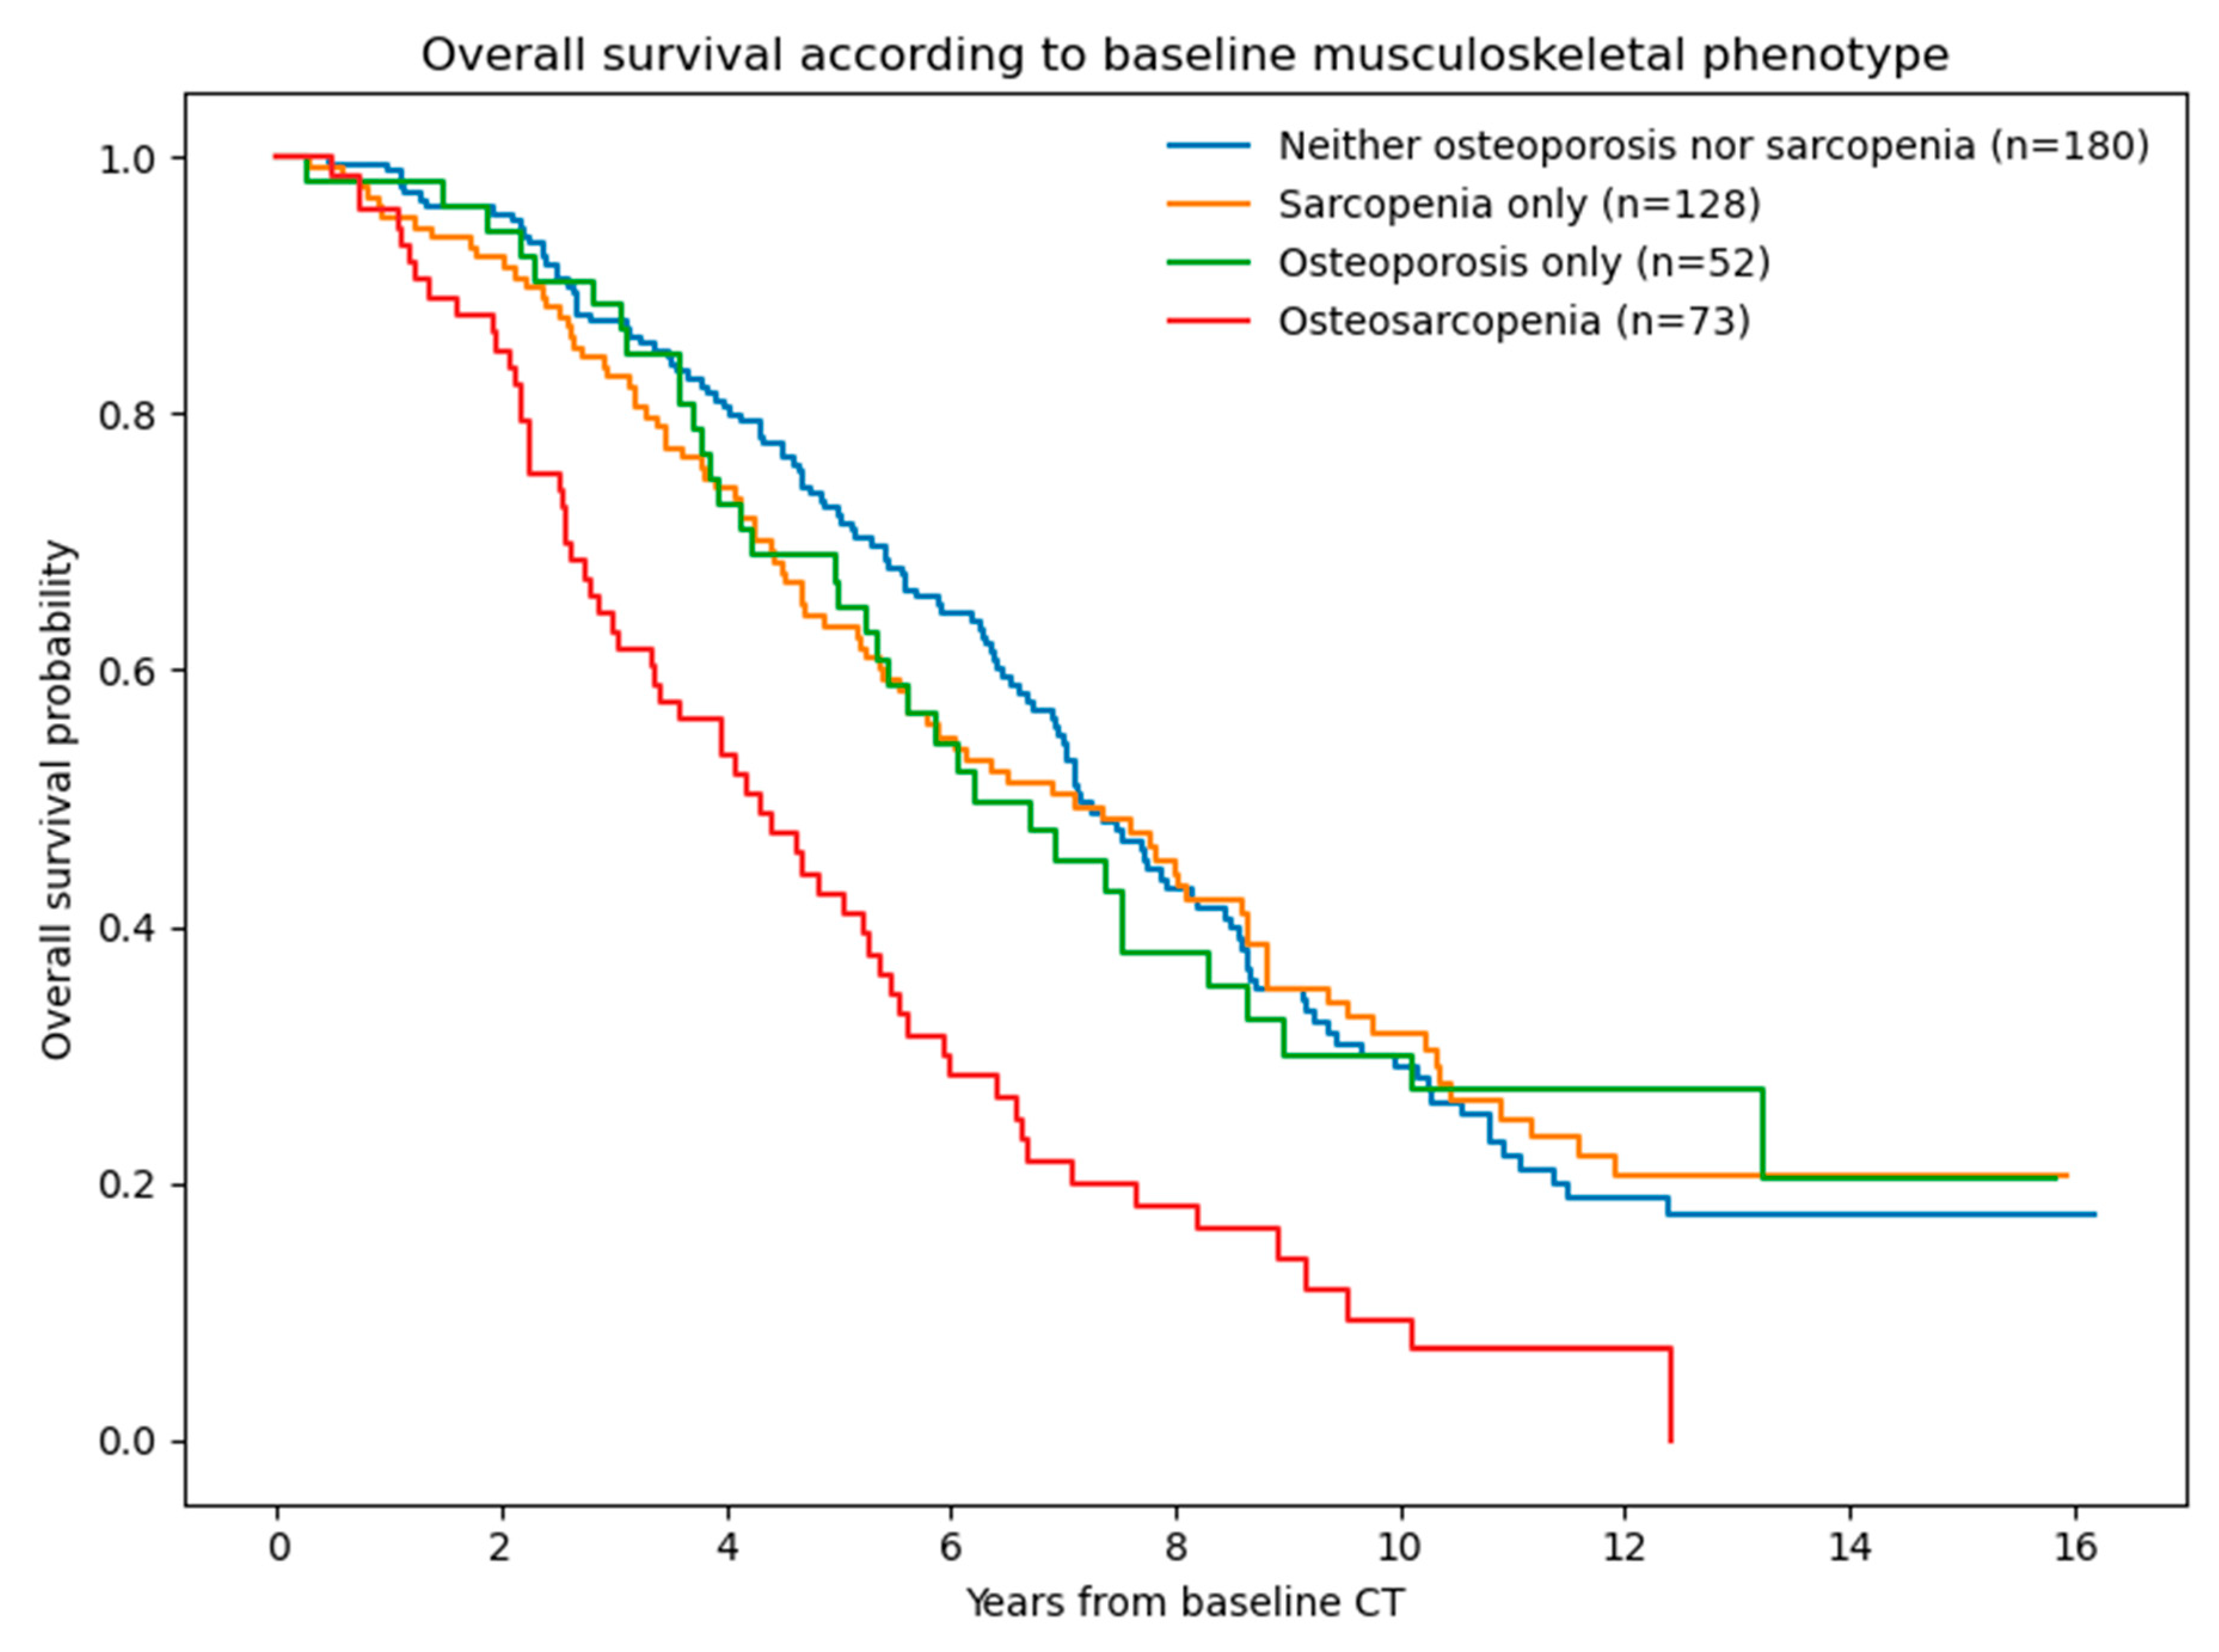

Table 1.
Patient characteristics as summarized in the overall cohort and grouped based on their musculoskeletal status at their initial CT scan. P-values reflect differences between individual sub-groups.
Table 1.
Patient characteristics as summarized in the overall cohort and grouped based on their musculoskeletal status at their initial CT scan. P-values reflect differences between individual sub-groups.
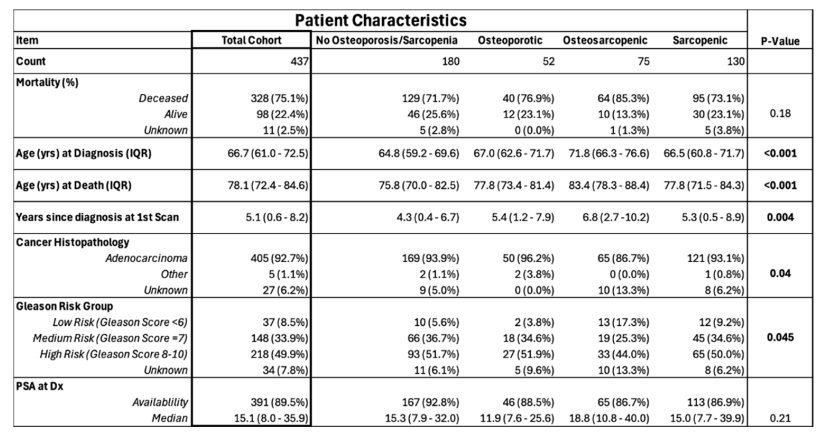 |
Table 2.
A: Corrected psoas muscle volume (cm³) by sub-group. B: Average BMD of L1-L5 by sub-group. C: Psoas muscle density classified by sub-group. D: Volumetric psoas muscle index (vPMI) by sub-group. HU = Hounsfield Units. HU < 135 used as criteria for osteoporosis diagnosis. vPMI < 30 used as criteria for sarcopenia.
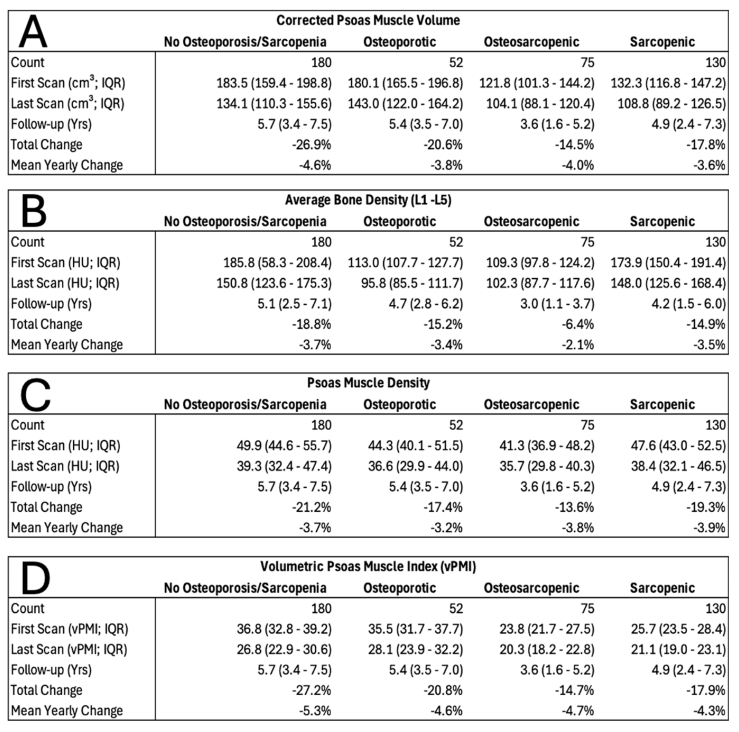 |
Table 3.
Multivariable Cox proportional hazards regression analysis of overall survival. Adjusted hazard ratios (HRs), 95% confidence intervals (CIs), and P-values are presented for age at first CT, years from prostate cancer diagnosis to first CT, log-transformed PSA at diagnosis, baseline osteosarcopenia status, and Gleason risk group. Overall survival was measured from the first available CT examination to death or administrative censoring. An HR > 1 indicates an increased hazard of death.
 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.