

Submitted:
20 September 2026
Posted:
20 September 2026
You are already at the latest version
Abstract
Early weight-loss responses to oral glucagon-like peptide-1 (GLP-1) receptor agonists vary substantially, yet the longitudinal clinical characteristics associated with super-response remain incompletely understood. Here using de-identified electronic health records, we studied 9,287 GLP-1 receptor agonist (GLP-1 RA) treatment-naive patients with a prescription for oral Wegovy. Of 8,381 patients with an index weight, 3,011 had a follow-up weight recorded between 30 and 180 days (early clinical observation period) and were classified by their best percent weight change as non-responders (no loss), responders (>0–5% loss), strong responders (>5–10%), or super-responders (>10%). Body weight was traced back five years, and HbA1c, blood pressure, comorbidities, dose escalation, and phenotypes extracted from clinical notes using AI-augmented curation were compared across these treatment response groups. At treatment initiation, super-responders weighed less than non-responders (94.1 versus 101.7 kg; P<0.001). Five years before treatment, super-responders weighed 7.6% less than at the index date, compared with 0.8% less among non-responders (P<0.001 across groups). Super-responders subsequently lost 7.2% by day 60 and 11.4% by day 90, returning on average to their weight from five years earlier within two months. Age, sex, type 2 diabetes, HbA1c, and blood pressure did not differ across groups at treatment initiation, and neither HbA1c nor blood pressure differed one, two, or five years earlier. Super-responders more often reached significantly higher doses early in treatment than non-responders: approximately 37% versus 24% were prescribed >1.5 mg at day 30 (P=0.001), 16% versus 9% were prescribed >4 mg at day 60 (P=0.056), and 6% versus 2% were prescribed >9 mg at day 90 (P=0.022; Fisher's exact test). Systolic blood pressure at day 90 fell by 10.2 mmHg in super-responders versus 3.3 mmHg in non-responders (P=0.006 across groups; P=0.003 for trend). Among 1,978 phenotypes AI-curated from unstructured clinical notes, before the first prescription, severe obesity was documented in 19.4% of super-responders versus 36.1% of non-responders (P<0.001; q=0.003). Super-responders had more pretreatment documentation of disordered eating (7.9% versus 3.1%) and less sleep-disordered breathing (35.2% versus 48.1%) and impaired fasting glucose (3.0% versus 7.5%) than non-responders, although differences were not significant after multiple-testing adjustment (all q≥0.26). Among GLP-1 RA-naive patients initiating oral Wegovy, greater early weight-loss response was associated with a more strongly rising weight trajectory over the preceding five years rather than with baseline glycemic or hemodynamic characteristics. In this observational study, pre-treatment weight trajectory and dosage emerged as associates of early oral semaglutide response, but the outcome-defined groups and short follow-up make these findings hypothesis-generating and warrant prospective validation.
Keywords:
oral semaglutide
; GLP-1 receptor agonists
; obesity
; early weight-loss response
; super-responders
; pretreatment weight trajectory
; dose escalation
Introduction
More than one billion people worldwide, adults and children together, now live with obesity [1]. Incretin-based therapy has set the reference for medical weight loss: once-weekly semaglutide 2.4 mg produced 14.9% mean weight loss over 68 weeks [2] and tirzepatide 15.0% to 20.9% across doses [3]. Oral semaglutide is the first of these agents available as a pill for weight management. At 25 mg once daily it produced 13.6% mean weight loss over 64 weeks in OASIS 4 [4], and the Food and Drug Administration approved the 25 mg tablet for chronic weight management on 22 December 2025, with a titration schedule through 1.5, 4 and 9 mg to the 25 mg maintenance dose. An oral route removes the injection as a barrier to initiation and is expected to bring a broader population to treatment than the injectables did.
The response to these drugs is heterogeneous. In STEP 1, 86% of participants on semaglutide lost at least 5% of body weight, 69% at least 10% and 51% at least 15%, so that one participant in seven did not reach the threshold that regulators and guidelines treat as clinically meaningful [2,5,6]. A 5% loss improves cardiovascular risk factors and a 10% loss improves them further [7], and these two thresholds define the response categories used across the field [8]. What distinguishes the patients at the two ends of the distribution is only partly understood. Type 2 diabetes attenuates weight loss [9,10], women lose more than men [11], early weight loss in the first weeks predicts the eventual response [12,13], and in routine care treatment for diabetes rather than obesity, a lower dose and lapses in coverage predict smaller loss [14,15]. Phenotype-guided selection of antiobesity medication has been proposed on the basis of eating behavior and energy expenditure [16].
One dimension that trials cannot examine is the weight history before treatment. Trial participants are enrolled at a single weight, in STEP 1 after excluding anyone who reported a change of more than 5 kg in the preceding 90 days2, and the years of gain or loss that brought them to that weight are self-reported at best. Electronic health records hold measured weights across a decade of routine visits, and they hold them for every patient who is later prescribed the drug. We previously described super-responders to the injectable GLP-1 RAs, defined there as more than 15% loss in the first year, and noted that the patients with minimal loss had nearly flat weight trajectories before treatment [17]. Whether the patients who go on to lose the most weight on an oral GLP-1 RA arrive on a different weight trajectory from those who lose none, in a population with no prior incretin exposure, and whether their glycemic and hemodynamic state differs in the years before treatment, has not been examined.
Here we studied GLP-1 RA naive patients starting oral Wegovy in routine care, classified them by their best weight change within 180 days into non-responders, responders, strong responders and super-responders, and traced body weight, glycated hemoglobin and blood pressure back over the five years before the first prescription. We report the pre-treatment hallmarks of each group, how weight and blood pressure moved after treatment began, and, in a supplement, the same analysis for the small early cohort starting orforglipron, an oral small-molecule GLP-1 RA approved in April 2026 [18].
Methods
Data source
We conducted a retrospective observational study of de-identified electronic health record (EHR) data accessed through the nference federated system. The study population comprised every patient with a prescription record for any GLP-1 RA through July 2026. Demographics, diagnoses, prescription records, vital signs and laboratory results were used. Prescription records defined the exposure and the index date; a prescription record established that a product was prescribed and did not establish that it was taken.
Study population
Oral Wegovy was defined as oral semaglutide at 1.5, 4, 9 or 25 mg, with the Wegovy brand recorded. The index date was the first qualifying prescription. Patients were GLP-1 RA naive if no prescription for semaglutide, tirzepatide, liraglutide, dulaglutide, exenatide, lixisenatide or orforglipron in any formulation appeared in the record before the index date. Patients with prior exposure were classified by the most recent product and excluded from the present analysis: injectable semaglutide or tirzepatide within 365 days before the index date, another oral GLP-1 RA, another GLP-1 RA, or any GLP-1 RA more than 365 days before the index date only. No age restriction was applied (47 of the 8,381 patients with an index weight were under 18 years old at the index date). A small number of qualifying prescriptions (46 patients) were dated before the month of approval and were retained. The same rules were applied to orforglipron (Foundayo).
Body weight
Body weight was taken from structured records. The index weight was the reading nearest the index date within the window from 180 days before to 7 days after it, with ties resolved to the pre-index value. Weight at each follow-up timepoint (30 to 240 days in 30-day steps) was the median of readings within 15 days of the timepoint. Weight before the index date was summarized at 90 days (median within 15 days), at 180, 365, 545 and 730 days (median within 45 days) and at each whole year from three to five years before the index date (median within 90 days). A window that contained the index reading itself was left empty for that patient. Every value is expressed as the percent change from the index weight, so that a negative value before the index date means the patient weighed less than at the start of treatment. The day-210 mean in the whole-cohort trajectory was replaced by the average of the day-180 and day-240 means because the window held few patients and a single outlying reading displaced it; its patient count and standard error are the observed ones. Follow-up was summarized as the days from the index date to the latest recorded weight.
Responder groups
Each patient's best response was the most negative percent change across the follow-up windows from 30 to 180 days. Patients were classified by that value into non-responders (no loss; best change at or above 0%), responders (loss of more than 0% and up to 5%), strong responders (more than 5% and up to 10%) and super-responders (more than 10%). The 5% and 10% boundaries are the thresholds at which weight loss is considered clinically meaningful in regulatory guidance, clinical guidelines, the phase 3 trials of the class and real-world comparisons [2,5,6,8,19]. A group was assigned to every patient with a reading in at least one window at or after day 30, and membership was fixed once assigned. Because the groups are defined on the post-index weights, the separation of their trajectories after the index date is definitional; the pre-index trajectories are not conditioned on anything and are the substantive comparison.
Glycated hemoglobin and blood pressure
HbA1c and systolic and diastolic blood pressure were taken from structured records. The index value and the value in each pre- and post-index window were defined with the same rules as for weight, and each window value is the within-patient change from the index value. For the baseline table the level itself is reported at the index date and as the median in the windows one, two and five years before it. Home blood pressure monitoring, where present, was excluded.
Baseline characteristics
Age, sex and race were taken from demographics. Type 2 diabetes was any qualifying diagnosis code (ICD-10 E11 or ICD-9 250) on or before the index date. Twenty-one comorbidities were defined by International Classification of Diseases (ICD) ICD-10 and ICD-9 code prefixes as any qualifying code on or before the index date. Baseline medication use was defined as at least one prescription of the class within 365 days before or on the index date, for metformin, SGLT2 inhibitors, ACE inhibitors or ARBs, beta blockers, calcium-channel blockers and diuretics; the drug and product names defining each class are listed in Table S1, and a record naming drugs from two classes was counted in both. New prescriptions of these classes after the index date were counted among patients whose record extended past day 90, to check whether a medication change rather than treatment could account for the blood-pressure course.
LLM-curated dosage extraction and dose escalation analysis
The prescribed strength was taken from the structured dose field of the prescription record where one was present. Where it was absent, the dose, brand and route were extracted from the free-text medication description with a large language model-assisted dose-mapping workflow based on GPT-OSS-20B, and the normalized strength was matched to the labeled oral Wegovy increments of 1.5, 4, 9 and 25 mg. Manual review of 74 unique medication descriptions confirmed correct dose assignment in every case; the only ambiguities (4 descriptions, 5.4%) were descriptions naming a titration sequence with several strengths (for example 'start 1.5, 4 mg then 9 mg'), which were assigned the highest strength listed as a convention. Descriptions carrying no strength (for example 'semaglutide tablet') were left without a dose and did not qualify a record. Across the oral Wegovy cohort a dose was resolvable for 99.8% of prescription records, and 99.7% of initiators had a dose recorded on their first prescription.
Oral Wegovy is titrated through 1.5, 4 and 9 mg to the 25 mg maintenance dose in 4-week steps, so that under the label a patient is on 4 mg at day 30, 9 mg at day 60 and 25 mg from day 85. Dose escalation was described at landmarks of 30, 60, 90 and 120 days after the index date. At each landmark the prescribed dose was the strength of the last oral Wegovy prescription written on or before that day, banded as 1.5 mg, 4 mg, or 9 or 25 mg. Because a patient whose record ends before the landmark cannot show an escalation, every landmark analysis was restricted to patients whose record demonstrably extended past it, with a prescription, weight or diagnosis dated on or after the landmark day. Weight change after the landmark was summarized by dose stratum at each later timepoint, together with the share of patients who had lost at least 5% and at least 10%, and compared across the three ordered strata by ANOVA with a linear-trend contrast. Time to each strength was the number of days from the index date to the first prescription of that strength.
Phenotypes extracted from clinical notes
Phenotypes documented in clinical notes were obtained with the AI-augmented-curation system [17,20,21,22,23,24], a set of clinical language models that reads every sentence of every note, recognizes disease and symptom mentions, and classifies each mention as affirmed, negated, suspected or family history with a probability. For each of the 3,011 classified patients, every mention in a note dated on or before the index date was used, anywhere in the patient's available record with no look-back limit, the same pre-index window as the comorbidities in Table 1. A phenotype was present for a patient if at least one of its mentions was classified as affirmed with a probability of 0.8 or higher. Mention names were mapped to a curated vocabulary of canonical phenotype names, and where the vocabulary holds several names for one clinical concept (for example morbid obesity and class III obesity, or the terms for hepatic steatosis) the names were combined into one concept, present if any member name was present; names denoting distinct constructs, such as documented disordered eating and a diagnosis of eating disorder, were kept separate. Of 12,523 distinct phenotypes present in at least one patient, 29 generic descriptors (for example 'illness' or 'complaint') were removed, and the 1,978 phenotypes present in at least 30 patients, comprising 1,968 single names and 10 combined concepts, were compared across the four responder groups by the chi-square test, with Benjamini-Hochberg (BH) correction across all 1,978 comparisons; q-values are reported. Table 2 presents the phenotypes relevant to obesity that structured diagnosis codes rarely carry.
Statistical analysis
Continuous variables are reported as mean (standard deviation, SD) and trajectories as mean with one standard error (SE). Differences across the four ordered responder groups were tested by one-way analysis of variance (ANOVA), and a linear trend across the groups in their order from non-responders to super-responders was tested by a contrast with equally spaced scores; binary characteristics were compared by the chi-square test. The two oral products in the supplement were compared by two-sided Welch t-tests. All tests are two-sided. P-values are unadjusted except for the note-derived phenotypes, where they were adjusted by the Benjamini-Hochberg procedure across the 1,978 phenotypes tested and are reported as q-values; the comparisons of pre-index weight at one, two and five years were the primary comparisons, and the comorbidity and dose rows of the baseline table are descriptive. Cells with fewer than 11 patients are reported as <11, and a trajectory point resting on fewer than 11 patients is drawn as an open marker with its value shown. Error bands in the figures denote one SE unless a caption states otherwise.
Statistical analysis plan for study advancement
The analytic approach followed established pharmacoepidemiologic and biostatistical conventions, and the study is reported in accordance with the STROBE and RECORD frameworks [25,26]. The design is a single-arm new-user cohort in which every patient starts the same drug at the same point in their treatment history (no prior GLP-1 RA), so that the comparison across responder groups is not confounded by prior incretin exposure or by the choice of product [27]. The responder thresholds (5% and 10%) and the 180-day window over which the best response was taken were fixed before the groups were formed and were drawn from the thresholds in use across the field [2,5,6]. Continuous measures were compared by ANOVA with a linear-trend contrast and binary measures by the chi-square test, without correction for multiplicity; the three pre-index weight comparisons are the primary analysis and every other row of the baseline table is disclosed as descriptive. Three choices were made after first results had been seen and are disclosed as such: the rule that any post-index reading at or after day 30 suffices to assign a group (an earlier draft required a day-180 reading, which left 71 patients); the extension of the pre-index weight history from two years to ten; and the presentation of HbA1c and blood pressure as within-patient change from the index value rather than as levels, adopted because the level trajectories were dominated by the different composition of the groups at each timepoint. The groups are defined on the outcome, so the post-index separation is by construction and every result should be read as hypothesis-generating.
De-identification and HIPAA compliance certification
Prior to analysis, all EHR data were de-identified under an expert determination consistent with the Health Insurance Portability and Accountability Act (HIPAA) Privacy Rule (45 CFR §164.514(b)(1)). The de-identification methodology employed a multi-layered transformation approach to both structured and unstructured data fields [28,29]. In structured data, direct identifiers including patient names and precise geographic locations were excluded entirely, while indirect identifiers underwent specific transformations: patient identifiers, medical record numbers, and accession numbers were replaced with one-way cryptographic hashes using confidential salts to preserve linkage across patient encounters; all dates were shifted backward by patient-specific random offsets (1–31 days) to preserve temporal relationships while obscuring exact event timing; the ZIP codes were truncated to two-digit state-level resolution; and continuous variables including age, height, weight, and body mass index (BMI) were thresholded to prevent identification of extreme values (for example, ages ≥89 years transformed to ‘89+’ and BMI >40 transformed to ‘40+’). In clinical text, an ensemble de-identification system that combines attention-based deep learning with rule-based methods achieved an estimated >99% recall for personally identifiable information (PII) detection, with detected identifiers replaced by plausible fictional surrogates. nference established secure data environments within each participating center, specifically designed to enable data access and analysis without requiring Institutional Review Board oversight, approval, or exemption confirmation. Accordingly, informed consent and IRB review were not required for this study.
Data harmonization
To address heterogeneity in EHR data, we harmonized clinical variables including medications, anthropometric measurements, and diagnoses to standardized concepts. For medications, we first constructed a standardized drug concept database combining the nference knowledge graph with RXNorm (https://www.nlm.nih.gov/research/umls/rxnorm/index.html) hierarchies to capture ingredient, brand, and dose-specific information. Medication records were matched using a hierarchical approach prioritizing RXNorm codes when available, followed by ingredient-level matching, and finally natural language processing and pattern matching on free-text medication orders when structured codes were absent. For anthropometric measurements (height, weight, BMI), we created a unified vocabulary from SNOMED (https://www.snomed.org/, https://athena.ohdsi.org) and LOINC (https://loinc.org/) and matched EHR measurement descriptions using standardized text matching algorithms with abbreviation expansion and synonym resolution; ambiguous mappings were resolved using OpenAI GPT-4o (https://platform.openai.com/docs/models/gpt-4o) with summary statistics as context, followed by manual verification. For diagnoses, we developed a hierarchical disease concept database from the knowledge graph and matched EHR diagnosis by identifying the most specific common child concept in the hierarchy. This approach enabled consistent identification of clinical entities while preserving granularity where available.
Results
Cohort derivation, baseline characteristics, and weight availability
Among 750,846 patients with a prescription record for any GLP-1 RA, 20,251 had at least one prescription for oral Wegovy. Of these, 10,964 had prior GLP-1 RA or dual glucose-dependent insulinotropic polypeptide (GIP)/GLP-1 receptor agonist exposure and were excluded: 4,295 had received injectable semaglutide and 3,739 tirzepatide within the preceding year, 271 another oral GLP-1 RA, 190 another GLP-1 RA, and 2,469 a GLP-1 RA more than a year before the index date only. The 9,287 GLP-1 RA naive initiators had a mean age of 53.6 years, 70.8% were female, and mean BMI was 33.8 kg/m². First prescriptions were dated from December 2025 through July 2026. A weight was recorded at the index date for 8,381 (mean 97.7 kg).
Follow-up was short: 3,438 of these patients had no weight recorded after the index date, and the 4,943 who did had their latest weight a mean of 47 days after it. Of those 4,943, the 3,011 with a weight in at least one follow-up window between 30 and 180 days could be classified by response, and the remaining 1,932 had post-index weights only outside the windows. Weight before the index date was available for a substantial minority at every timepoint: 3,687 (44.0%) of the 8,381 had a weight in the window one year before, 3,148 (37.6%) two years before, 2,877 (34.3%) five years before and 1,863 (22.2%) ten years before. Among the 3,011 classified patients, who by definition have both an index weight and a follow-up weight, 1,502 (49.9%) also had a weight one year before the index date and 1,169 (38.8%) five years before index (Figure 1, Figure S1).
Figure 1.
Hallmarks of oral Wegovy super-response.(A) Derivation of the GLP-1 receptor agonist (GLP-1 RA)-naive oral Wegovy cohort. Of 9,287 eligible initiators, 8,381 had an index weight and 3,011 had a follow-up weight recorded between days 30 and 180. Patients were classified by their best percentage weight change within 180 days as non-responders (no loss), responders (>0–5% loss), strong responders (>5–10% loss), or super-responders (>10% loss). The index date was the first oral Wegovy prescription. (B) Schematic comparison of pretreatment weight gain and on-treatment weight loss. Five years before initiation, super-responders weighed 7.6% less than their index weight, compared with 0.8% less among non-responders (P<0.001 across groups). Super-responders lost 7.2% by day 60 and 11.4% by day 90, returning approximately to their weight from five years earlier within two months. Silhouettes are illustrative and are not scaled to measured body dimensions; “no weight loss” denotes the non-responder group definition. (C) Distributions of prescribed oral Wegovy doses from days 30 to 180 among non-responders and super-responders. Blue shades indicate 1.5-, 4-, 9-, and 25-mg doses; orange outlines identify the dose expected under the labeled escalation schedule. Percentages are rounded or approximate as displayed in the source data. (D) Mean systolic blood pressure change at day 90 was −10.2 mmHg in super-responders and −3.3 mmHg in non-responders (P=0.006 across all four groups; P=0.003 for trend). Age, sex, type 2 diabetes, HbA1c, and blood pressure did not differ across groups at initiation; HbA1c and blood pressure also did not differ one, two, or five years earlier. Findings reflect observational associations in outcome-defined groups with short follow-up and require prospective validation.
Figure 1.
Hallmarks of oral Wegovy super-response.(A) Derivation of the GLP-1 receptor agonist (GLP-1 RA)-naive oral Wegovy cohort. Of 9,287 eligible initiators, 8,381 had an index weight and 3,011 had a follow-up weight recorded between days 30 and 180. Patients were classified by their best percentage weight change within 180 days as non-responders (no loss), responders (>0–5% loss), strong responders (>5–10% loss), or super-responders (>10% loss). The index date was the first oral Wegovy prescription. (B) Schematic comparison of pretreatment weight gain and on-treatment weight loss. Five years before initiation, super-responders weighed 7.6% less than their index weight, compared with 0.8% less among non-responders (P<0.001 across groups). Super-responders lost 7.2% by day 60 and 11.4% by day 90, returning approximately to their weight from five years earlier within two months. Silhouettes are illustrative and are not scaled to measured body dimensions; “no weight loss” denotes the non-responder group definition. (C) Distributions of prescribed oral Wegovy doses from days 30 to 180 among non-responders and super-responders. Blue shades indicate 1.5-, 4-, 9-, and 25-mg doses; orange outlines identify the dose expected under the labeled escalation schedule. Percentages are rounded or approximate as displayed in the source data. (D) Mean systolic blood pressure change at day 90 was −10.2 mmHg in super-responders and −3.3 mmHg in non-responders (P=0.006 across all four groups; P=0.003 for trend). Age, sex, type 2 diabetes, HbA1c, and blood pressure did not differ across groups at initiation; HbA1c and blood pressure also did not differ one, two, or five years earlier. Findings reflect observational associations in outcome-defined groups with short follow-up and require prospective validation.
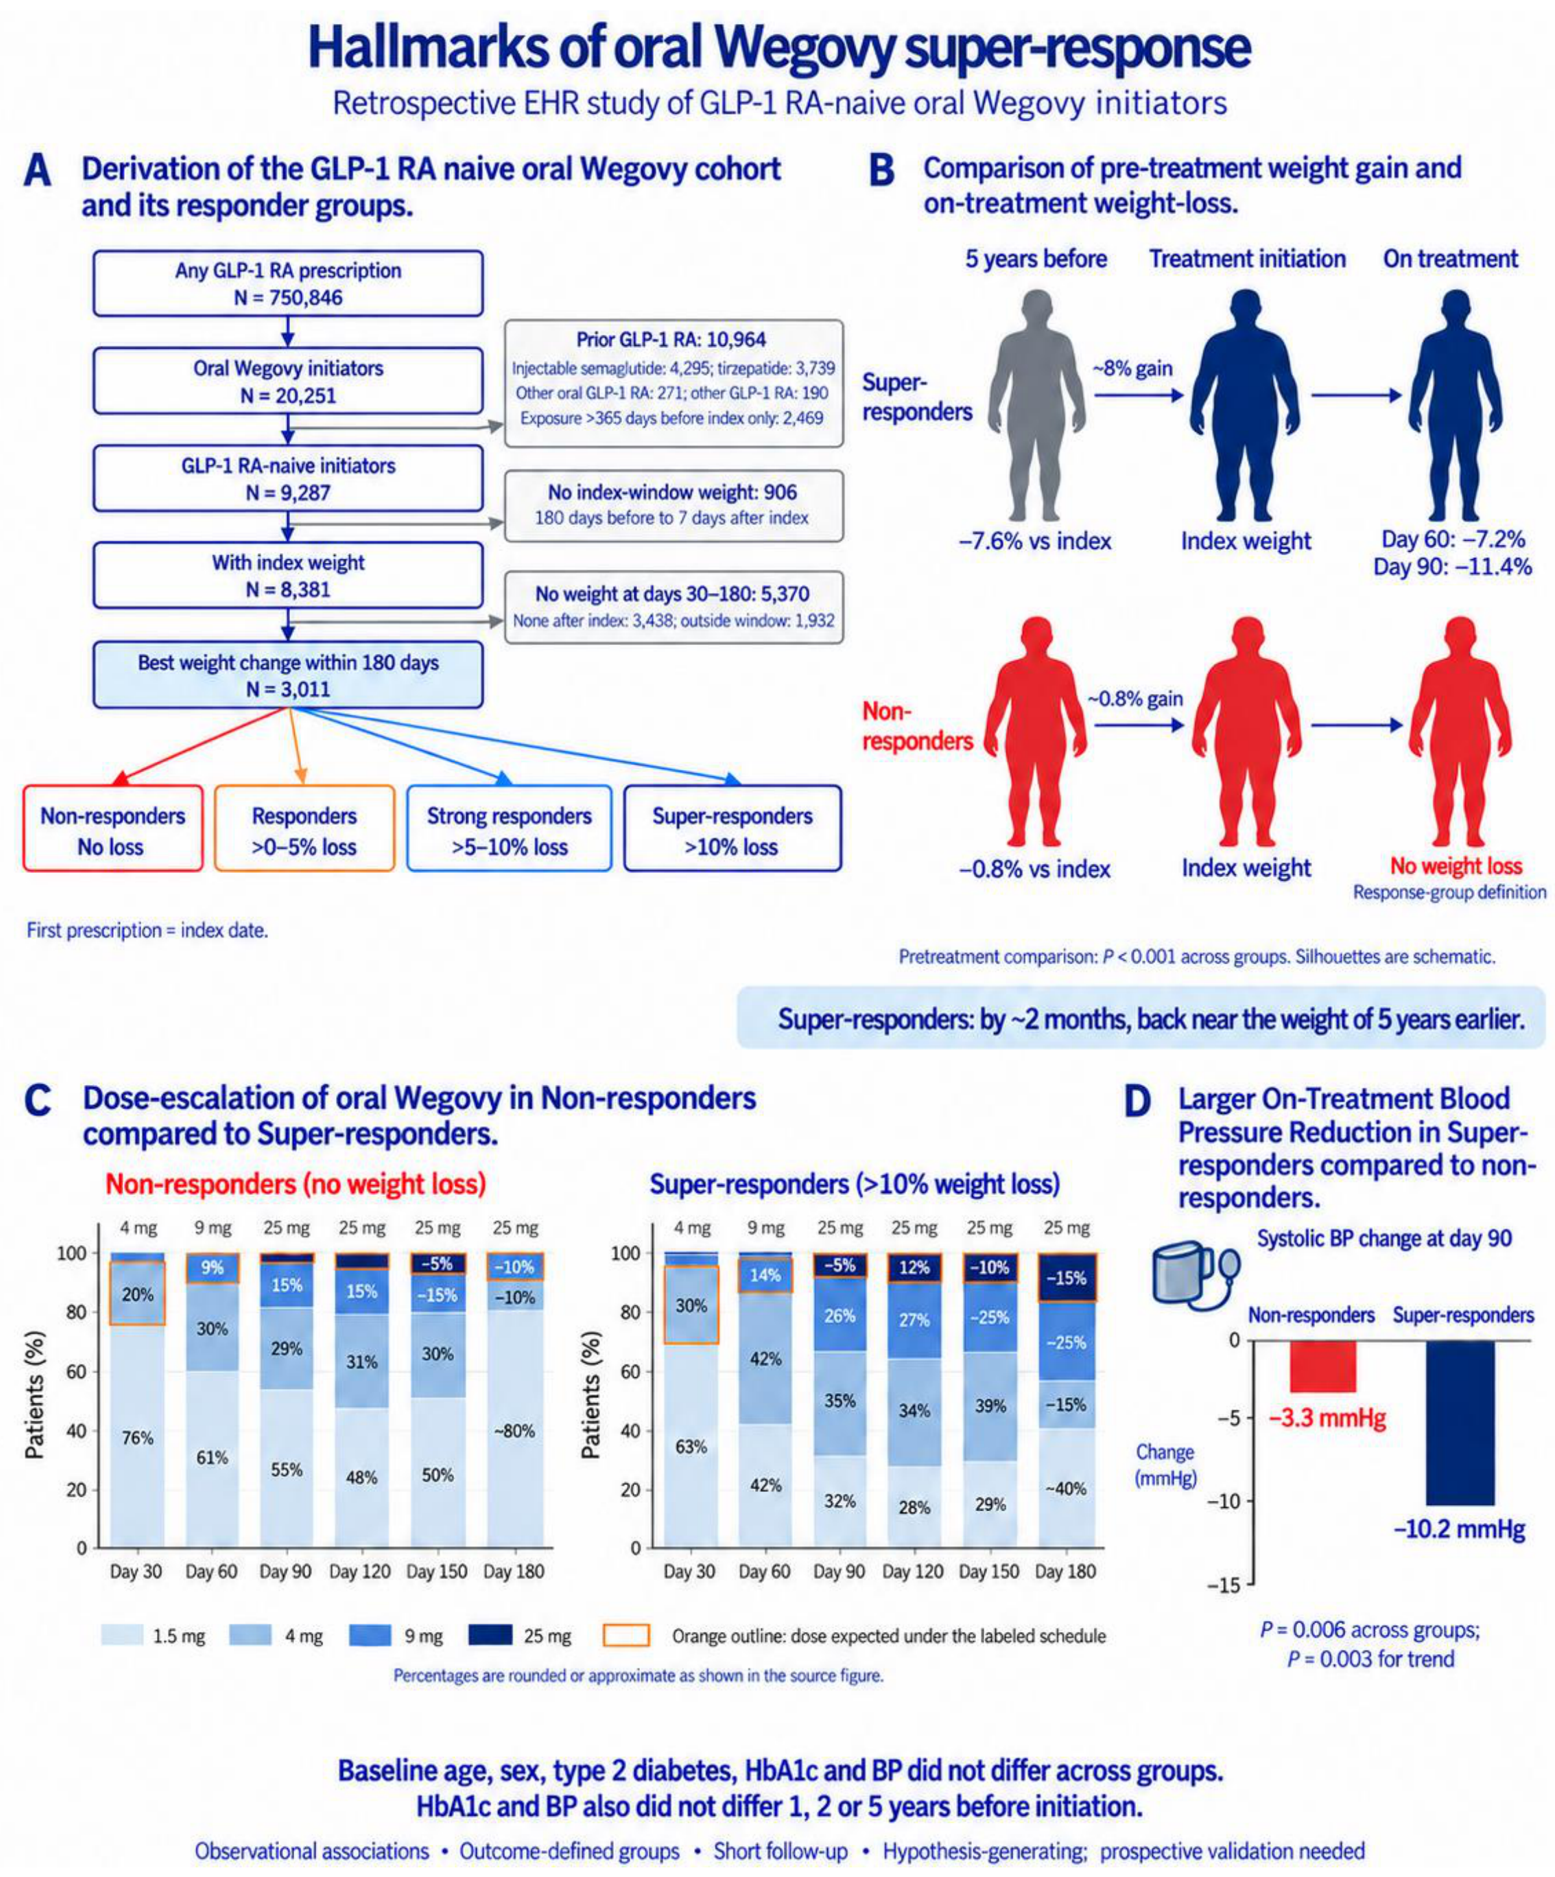
Weight-loss outcomes on oral Wegovy accrued through the initial titration period and was significantly heterogeneous
Each post-index mean is taken over the classified patients with a weight in that window. Mean weight change was −1.1% at day 30 (N=1,810 patients), −2.1% at day 60 (N=1,205), −3.3% at day 90 (N=973), −4.1% at day 120 (N=530) and −5.5% at day 180 (N=71). Retrospective pre-treatment weight trajectory analysis, drawing on all 8,381 patients with an index weight, showed that the overall cohort had gained weight before initiation of oral Wegovy: mean weight was 1.8% below the index weight one year earlier (N=3,687 patients) and 3.5% below it five years earlier (N=2,877). The share of patients who had lost at least 5% was 6.7% at day 30, 19.5% at day 60, 29.8% at day 90 and 45.1% at day 180 (71 patients), and the share who had lost at least 10% was 7.0% at day 90 and 23.9% at day 180 (Figure 2).
Weight-loss Super-responders to Oral-Wegovy had gained about 8% of their body weight over the five years before GLP-1 therapy, while non-responders had been weight-stable
Weight loss was widely dispersed across patients: the best change within 180 days averaged −2.8% (SD 4.7), with individual patients ranging from weight gain to losses beyond 15% (Figure 3). On this distribution, patients were stratified based on their post-treatment weight trajectories (see Methods), into 750 non-responders (24.9%), 1,547 responders (51.4%), 549 strong responders (18.2%) and 165 super-responders (5.5%). The four groups did not differ in average age (53.3, 54.5, 53.8, 51.5 years; P=0.065), sex (71.2, 74.5, 76.9, 74.5% female; P=0.13) or documented baseline type 2 diabetes prevalence (7.9, 6.5, 4.9, 5.5%; P=0.18). There were differences in weight and BMI at the index date, with significantly lower weight in super-responders compared to non-responders (mean weight 94.1 versus 101.7 kg, P<0.001) and decreasing BMI across increasing response strata (34.9, 34.1, 33.5, 33.0 kg/m2; P<0.001) (Table 1).
Figure 3.
Weight trajectories and LLM-curated dose escalation of the four oral Wegovy weight-loss responder outcome groups. (A) Weight trajectories from five years before to 180 days after the first oral Wegovy prescription (N=3,011; 750 non-responders, 1,547 responders, 549 strong responders, 165 super-responders). Each point is the mean percent change from the index weight among patients in the group with a reading in that window; a negative value before the index date means the patient weighed less then than at the start of treatment. The post-index separation is definitional, because the groups were formed on those values; the pre-index paths are the substantive comparison. Weight was collected ten years before the index date and is shown to five. The pre-index axis is compressed. Points resting on fewer than 11 patients are drawn as open markers. (B) Distribution of each patient's best percent change within 180 days (N=3,011), in one-point bins colored by responder group, with the mean marked; negative values are loss. (C) Prescribed dose at day 60 and at day 90 (the strength of the last prescription written on or before that day), by responder group, as a share of the classified patients whose record extended past the landmark, with the number of patients under each bar. (D) Mean percent weight change at day 120 by the prescribed dose at day 60 and at day 90, among patients observed past the landmark with a weight at day 120; error bars denote one SE, and the share who had lost at least 5% by day 120 is printed under each mean. Light blue, 1.5 mg; blue, 4 mg; navy, 9 or 25 mg.
Figure 3.
Weight trajectories and LLM-curated dose escalation of the four oral Wegovy weight-loss responder outcome groups. (A) Weight trajectories from five years before to 180 days after the first oral Wegovy prescription (N=3,011; 750 non-responders, 1,547 responders, 549 strong responders, 165 super-responders). Each point is the mean percent change from the index weight among patients in the group with a reading in that window; a negative value before the index date means the patient weighed less then than at the start of treatment. The post-index separation is definitional, because the groups were formed on those values; the pre-index paths are the substantive comparison. Weight was collected ten years before the index date and is shown to five. The pre-index axis is compressed. Points resting on fewer than 11 patients are drawn as open markers. (B) Distribution of each patient's best percent change within 180 days (N=3,011), in one-point bins colored by responder group, with the mean marked; negative values are loss. (C) Prescribed dose at day 60 and at day 90 (the strength of the last prescription written on or before that day), by responder group, as a share of the classified patients whose record extended past the landmark, with the number of patients under each bar. (D) Mean percent weight change at day 120 by the prescribed dose at day 60 and at day 90, among patients observed past the landmark with a weight at day 120; error bars denote one SE, and the share who had lost at least 5% by day 120 is printed under each mean. Light blue, 1.5 mg; blue, 4 mg; navy, 9 or 25 mg.
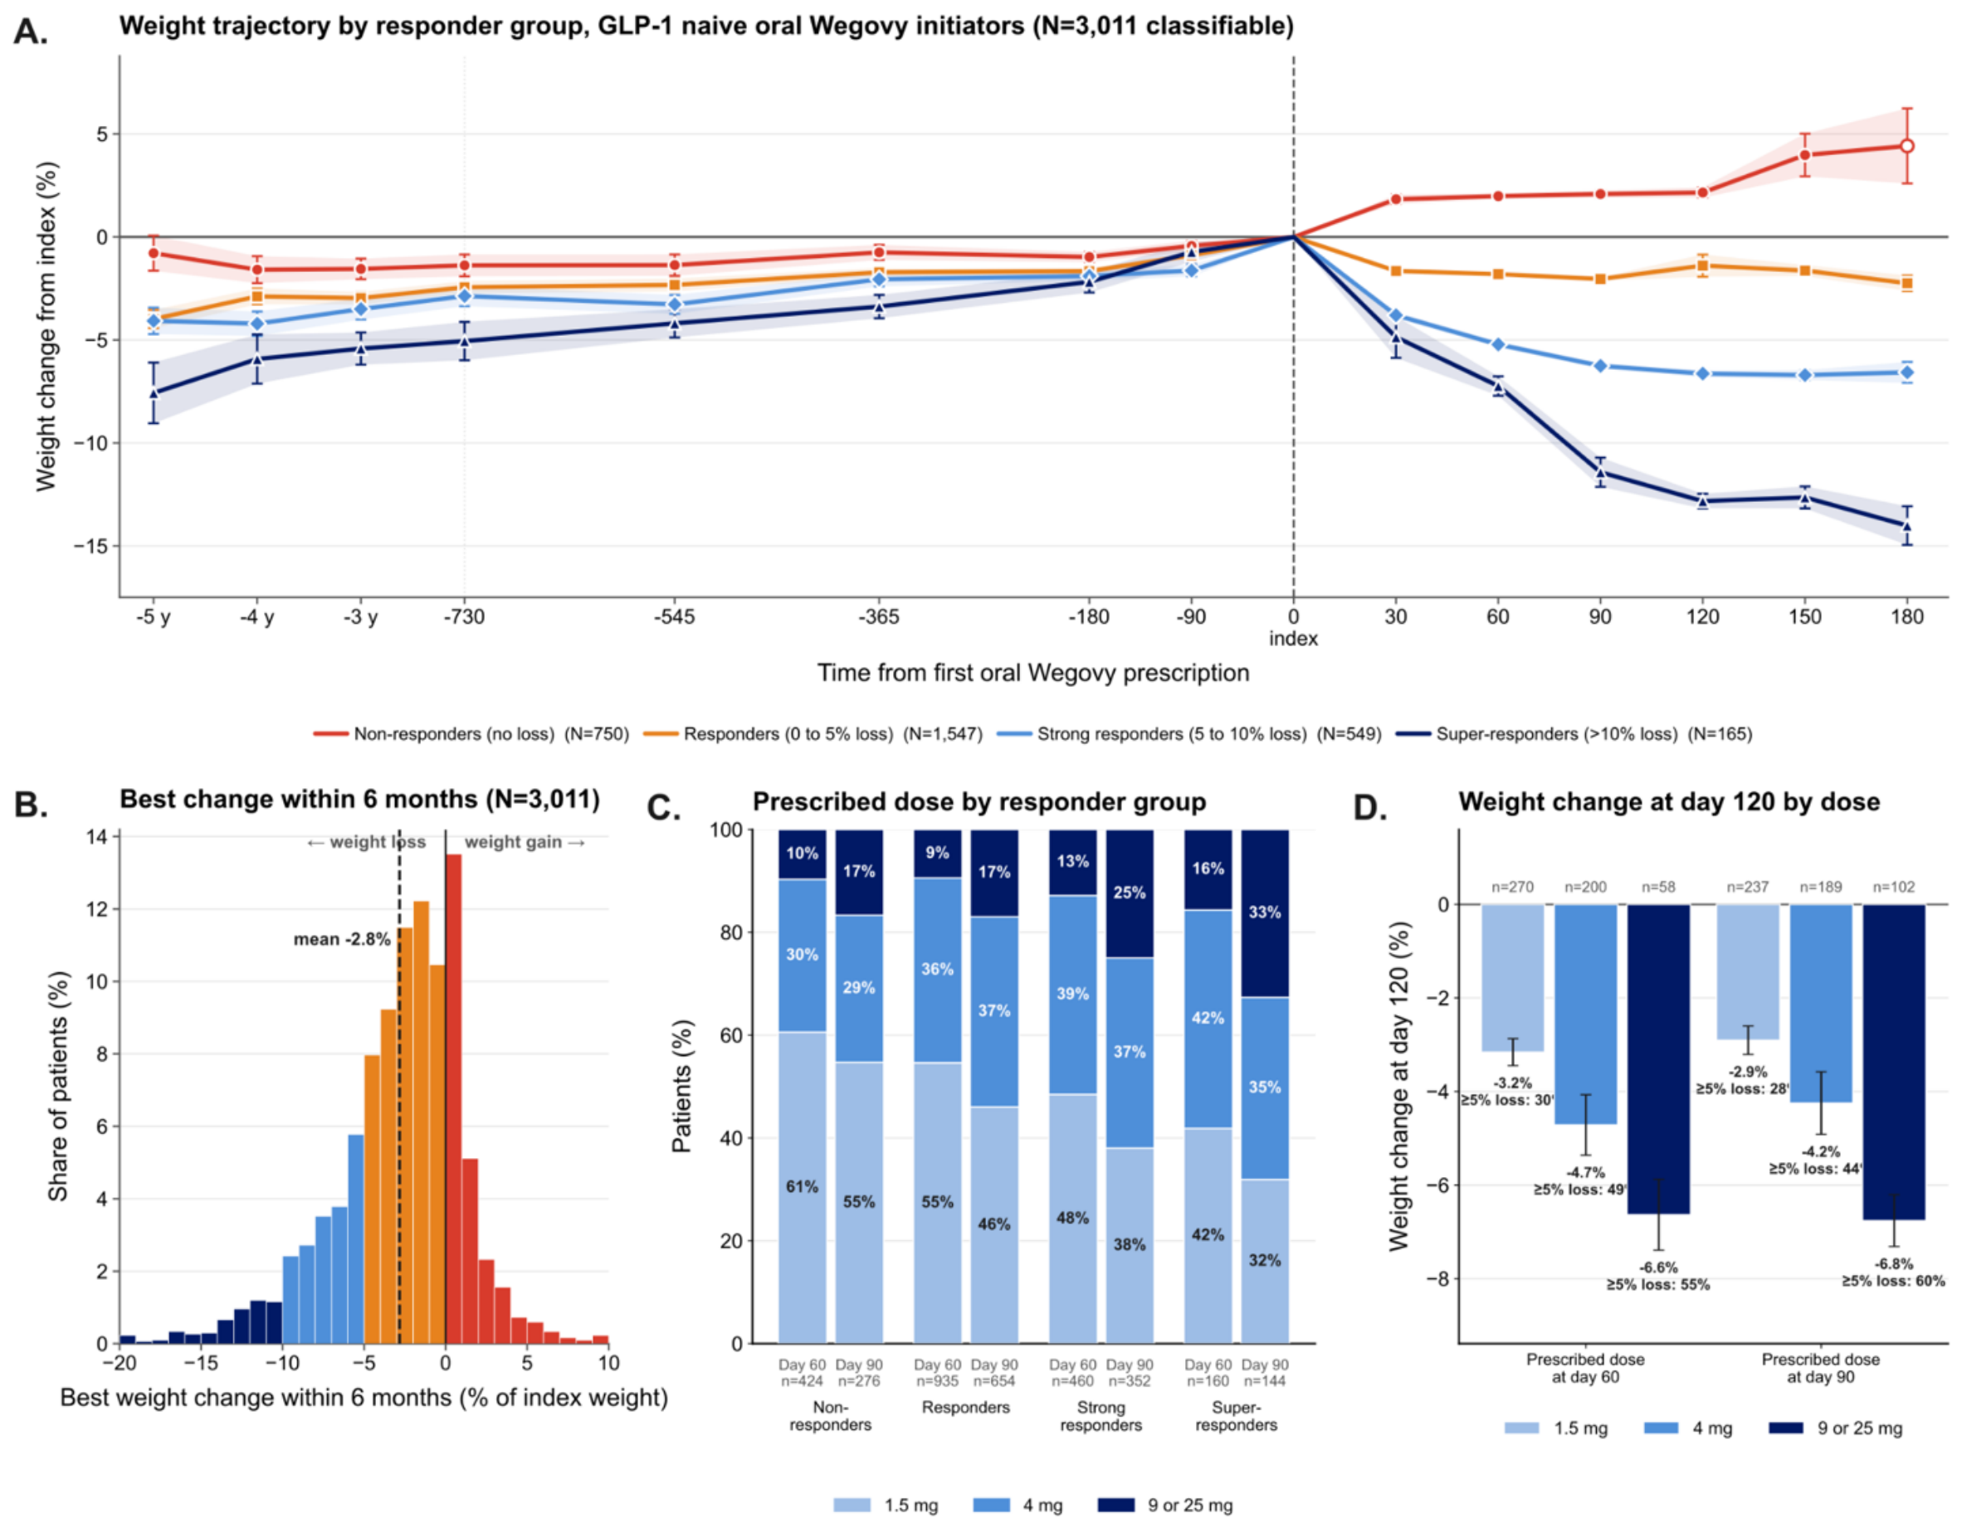
Before the index date, the four groups were on different weight paths. Five years earlier, super-responders had weighed 7.6% less than at the index date (N=64 patients; 38.8% of the group), strong responders 4.1% less (N=230, 41.9%), responders 4.0% less (N=621, 40.1%) and non-responders 0.8% less (N=254, 33.9%; P<0.001 across groups, P<0.001 for trend). These are within-patient changes, each relative to the patient's own index weight; the kilogram values in Table 1 for five years earlier describe the same subsets, whose index weights were lower than those of their groups as a whole (Figure 3, Table 1).
The gradient was also present at earlier timepoints. For example, two years before the index date, the groups had weighed 1.4, 2.4, 2.9, and 5.1% less than at index from non-responders to super-responders (P=0.007; P<0.001 for trend). One year before the index date, these values were 0.7, 1.7, 2.1, and 3.4% less (P=0.001; P<0.001 for trend) (Figure 3, Table 1).
After the index date the trajectories separated as defined by the stratification criteria. Super-responders achieved a weight change of −4.9% by day 30, −7.2% by day 60, −11.4% by day 90 and −12.8% by day 120 (N=74, 71, 96 and 80 patients). Taken in the context of the pre-treatment weight trajectories, this indicates that the average super-responder had returned to the weight recorded five years earlier by approximately day 60 after treatment initiation (−7.2% against −7.6%). Strong responders were at −6.3% and responders at −2.0% by day 90, while non-responders had gained 2.1% (Figure 3).
Oral Wegovy responder groups differed in LLM-curated dose escalation, as well as pre-existing index weight and select comorbidities, but not in pre-existing glycemic index or blood pressure
Super-responders weighed less and had lower BMI at the index date than non-responders (94.1 versus 101.7 kg; BMI 33.0 versus 34.9 kg/m²; both P<0.001), and they weighed less at each assessed earlier timepoint. Obstructive sleep apnea (28.0 / 23.1 / 21.9 / 15.8%; P=0.002), tobacco use (14.5 / 11.1 / 9.8 / 4.8%; P=0.001) and prediabetes (36.5 / 37.2 / 32.4 / 26.1%; P=0.012) were progressively less common from non-responders to super-responders. Heart failure (6.7 / 4.1 / 3.6 / 5.5%; P=0.025) and polycystic ovary syndrome (5.6 / 3.6 / 2.2 / 5.5%; P=0.010) were most common among non-responders without a monotonic gradient. Type 2 diabetes, hypertension, hyperlipidemia, coronary artery disease, depression, anxiety and the remaining comorbidities did not differ. Medication use in the year before the index date was balanced across the groups: metformin was prescribed for 9.5% to 12.1%, SGLT2 inhibitors for 1.6% to 3.0%, ACE inhibitors or ARBs for 28.5% to 29.5%, beta blockers for 18.0% to 22.0% and diuretics for 18.8% to 23.6%, with calcium-channel blockers slightly less common with increasing response (17.3% to 11.5%; P=0.048). New prescriptions of any of these classes in the first 90 days after the index date were rare, reaching at most 2.2% of any group for any class, and were no more frequent in the groups whose blood pressure fell most (Table 1).
Dose escalation was associated with treatment response. Among patients whose record extended past day 60, the the LLM-curated prescribed dose on that day was still the 1.5 mg starting dose for 60.6 / 54.7 / 48.5 / 41.9% of the four groups (P<0.001), so that 58.1% of super-responders and 39.4% of non-responders had escalated beyond it. The prescribed dose was 4 mg for 29.7 / 35.9 / 38.7 / 42.5% (P=0.009) and 9 or 25 mg for 9.7 / 9.4 / 12.8 / 15.6% (P=0.041); by day 90 the share on 9 or 25 mg was 16.7 / 17.0 / 25.0 / 32.6% (P<0.001). Follow-up time also correlated with response: the latest weight was recorded 61 / 67 / 99 / 125 days after the index date from non-responders to super-responders (P<0.001), a consequence of defining the groups based on maximum achieved weight loss (Table 1, Figure 3).
Escalation in routine care was slower than the label, and the weight loss that followed scaled with the dose reached. Of the 1,777 patients observed past day 90, 45.5% were still on 1.5 mg on that day, 33.8% were on 4 mg and 20.8% on 9 or 25 mg, although the label has every patient on 25 mg from day 85; among patients who did escalate, the first 4 mg, 9 mg and 25 mg prescriptions came a mean of 20, 39 and 46 days after the index date. Patients whose LLM-curated prescribed strength had reached 9 mg or 25 mg by day 90 went on to a mean weight change of −6.8% at day 120, against −4.2% for those on 4 mg and −2.9% for those still on 1.5 mg (n=102, 189 and 237; P<0.001; P<0.001 for trend), and 60%, 44% and 28% respectively had lost at least 5% by day 120. The prescribed dose at day 60 gave the same picture at day 120 (−6.6%, −4.7% and −3.2%; n=58, 200 and 270; P<0.001), and patients already moved to 4 mg by day 30 had lost −3.0% by day 60 against −1.8% on 1.5 mg (P<0.001). Beyond day 150 the strata were too thin to compare (Figure 3). The lag behind the label was present in every responder group and at every landmark. At day 90, when the label has every patient on 25 mg, 2% of non-responders, 4% of responders, 5% of strong responders and 6% of super-responders were on 25 mg, and 55%, 46%, 38% and 32% respectively were still on 1.5 mg; by day 120, 20% of non-responders and 39% of super-responders were on 9 or 25 mg (Figure 3, Figure S2).
Glycemic control and blood pressure were similar across the groups before treatment. Mean HbA1c at the index date ranged from 5-4-5.6% (P=0.16), and mean systolic and diastolic blood pressures were nearly identical across the groups at approximately 127 mmHg (P=0.86) and 77 mmHg (P=0.86), respectively. Further, none of these measurements differed significantly at one, two or five years before the index date (e.g., at five years: HbA1c P=0.73, systolic P=0.47, diastolic P=0.53) (Table 1).
AI-augmented curation of clinical notes place oral Wegovy super-responders at lower documented obesity severity and higher documented disordered eating before treatment
To look beyond structured diagnosis codes, phenotypes were extracted using AI-curation from every clinical note dated on or before the index date; 2,942 of the 3,011 classified patients had at least one such note. Of 12,523 distinct phenotypes documented in at least one patient, 1,978 were documented in at least 30 patients and were compared across the four groups, with false-discovery correction across all 1,978 comparisons.
Severe obesity was documented in 36.1% of non-responders, 31.5% of responders, 25.3% of strong responders and 19.4% of super-responders (P<0.001, q=0.003), consistent with the BMI gradient shown in Table 1. Impaired fasting glucose was documented in 7.5% of non-responders versus 3.0% of super-responders (P<0.001, q=0.26), and sleep-disordered breathing (including snoring and sleep apnea)in 48.1% versus 35.2% (P=0.005, q=0.32), corroborating the findings for coded diagnosis of sleep apnea (Table 1).
Among eating behaviors, disordered eating was documented in 7.9% of super-responders compared to 3.1% of non-responders, 3.0% of responders and 2.9% of strong responders (P=0.008, q=0.35); emotional eating was least often documented in super-responders (4.2%, against 7.5% of non-responders, 8.0% of responders and 10.6% of strong responders; P=0.043, q=0.72); and hunger was documented in 37.6% of non-responders, 40.5% of responders, 43.2% of strong responders and 43.0% of super-responders (P=0.20, q=0.82). Documented weight gain was more common in every responding group than in non-responders (60.0% of non-responders against 67.1% of responders, 68.9% of strong responders and 64.2% of super-responders; P=0.002, q=0.26). Fatty liver disease fell from 18.3% of non-responders to 16.2% of responders, 14.0% of strong responders and 12.1% of super-responders without reaching significance (P=0.098, q=0.74). Bipolar disorder or schizophrenia was least often documented in super-responders (3.6%, against 9.3% of non-responders, 7.6% of responders and 6.4% of strong responders; P=0.044, q=0.72); psychological trauma was most often documented at the two extremes (11.7% of non-responders and 12.7% of super-responders, against 8.1% of responders and 7.8% of strong responders; P=0.009, q=0.36); and perimenopause or menopause was most often documented in the two intermediate groups (23.5% of responders and 27.5% of strong responders, against 17.6% of non-responders and 18.8% of super-responders; P<0.001, q=0.09).
Taken together, the AI-augmented curation of clinical notes place super-responders at lower documented obesity severity, less sleep-disordered breathing and less glycemic impairment before treatment, and more often carry a documented history of disordered eating (Table 2).
Larger systolic blood pressure reductions accompanied greater weight-loss response
Within-patient change in blood pressure was flat before the index date in every group but diverged after treatment initiation. At day 90 after the index date, systolic pressure had fallen by 3.3 / 3.4 / 7.3 / 10.2 mmHg from non-responders to super-responders (N = 67 / 192 / 105 / 44 patients; P=0.006; P=0.003 for trend). The gradient was already present at day 30 (0.9 / 1.3 / 4.2 / 6.6 mmHg; P=0.025 for trend). Diastolic pressure at day 90 had fallen by 1.9 / 0.5 / 3.0 / 4.7 mmHg (P=0.033; P=0.059 for trend). HbA1c was recorded at the index date for 2,431 patients but after it for fewer than 11 per group at every timepoint. By day 90, HbA1c had fallen by 0.40 percentage points in non-responders and 0.55 in super-responders (N<11 in each group; P=0.71), with no significant difference across the four groups (P=0.75) (Figure 4).
Exploratory Analysis of Early Weight-Lo
ss Response to Foundayo
Over the same period 1,082 patients had a first prescription for orforglipron (Foundayo, approved on April 1, 2026), of whom 380 were GLP-1 RA naive, 332 had an index weight and 54 had a weight in at least one follow-up window between 30 and 180 days and could be classified: 19 non-responders (35.1%), 33 responders (61.1%), <11 strong responders, and no super-responders as of currently available early response data from the routine care setting.
This analysis should be viewed as hypothesis-generating, as follow-up was shorter for Foundayo than for oral Wegovy and 254 of the 332 patients had no weight recorded after the index date. Furthermore among the 78 patients who did have a weight recorded after their index date, the latest weight recorded was only a mean of 27 days after initiating Foundayo, in contrast to a mean of 47 days after initiating oral Wegovy, so it is likely that more Foundayo patients had not yet reached the first follow-up timepoint when their weight would be recorded.
The Foundayo weight-loss responder groups showed the same direction in pre-index weight as the oral Wegovy groups, with responders having weighed 6.4% less two years before the index date (N=16) while non-responders had weighed more than at index (N<11) (Figure 5).
Discussion
In this study, we explored early weight change patterns in GLP-1 RA naive patients starting oral Wegovy in routine care. There was significant heterogeneity in response, allowing stratification of patients into categorical groups of non-responders, responders, strong responders, and super-responders. Comparison of pre-treatment characteristics between these groups highlighted several interesting enrichments, including a higher rate of weight gain in the five years preceding treatment initiation among super-responders. Specifically, super-responders had gained about 8% of their body weight over the five years before the first prescription, non-responders had gained under 1%, and the two intermediate groups sat between them in order. After the first oral Wegovy prescription, the average weight of super-responders had returned to their weight from five years earlier within two months. Super-responders also weighed less on average at their time of initiation, while age, sex, and baseline glycemic control and blood pressure were not significantly different between the response categories. Systolic blood pressure fell in association with the weight response, by 10.2 mmHg at day 90 in super-responders compared to 3.3 mmHg in non-responders.
The difference in pre-index weight trajectories is an intriguing finding that could provide utility as a clinical biomarker and facilitate mechanistic hypothesis generation for further evaluation. These findings are in line with our previous analysis of real-world users of injectable semaglutide and tirzepatide, so this does not appear to be unique to the oral formulation. Whether it reflects a class effect related to invest in signaling or a broader weight plasticity phenomenon cannot be determined from this study. For example, it may be that weight recently gained can be more readily lost than weight held for years, due to the metabolic and behavioral adaptations, the fact that may reflect a transient perturbation (a medication, an illness, a change in circumstance), or other factors. This pattern has also been seen outside of pharmacotherapy. In a lifestyle program, participants who gained weight between screening and the first session lost the most in the first four weeks, and after bariatric surgery the patients who had gained weight before the operation lost the most from the operative weight [31,32]. The absence of any pre-index gradient in HbA1c or blood pressure suggests that the hallmark is the weight trajectory itself rather than the metabolic state it had produced.
Super-responders had a lower average weight at the index date and had weighed less at every assessed earlier timepoint. A meta-regression of 47 trials points the other way, with greater loss associated with higher baseline BMI [33]. This discrepancy warrants further investigation but could be related to selection bias or other factors influencing real-world utilization and effectiveness. Female sex has been associated with greater loss in trials [11,33], but sex did not differ across the four groups here. Super-responders also escalated their dose faster: at day 60, 58% were beyond the starting dose against 39% of non-responders. Faster escalation could be a driver of higher weight loss or a consequence of treatment success, as a patient who is losing weight and tolerating the medication is more likely to escalate on schedule. It is important to note that this study primarily captures weight loss occurring during the titration period. Most patients had been prescribed 1.5 or 4 mg through day 56, and few had reached the 25 mg maintenance dose within the observed follow-up. Thus, the 29.8% who had lost at least 5% by day 90 and the 45.1% by day 180 are early figures and not comparable to the 64-week response rates described in the OASIS 4 trial [4]. That early weight loss predicts the eventual response has been shown for liraglutide and tirzepatide [12,13], and the separation of the four groups within the first month here, before any group could have completed titration, is consistent with it. The higher proportion of patients with no observed weight loss in the Foundayo cohort than in the oral Wegovy cohort (35.2% vs 24.9%; Figure S3) is likely related to the shorter average follow-up time in the Foundayo cohort and should not be interpreted as a head-to-head comparison of these agents.There are several limitations of this study. First, it is a retrospective real-world analysis and thus is prone to multiple sources of selection, documentation, and ascertainment bias. Second, there was significant variability in follow-up time following treatment initiation, which likely contributed in part to the cohort definitions themselves. Specifically, because the categorical response groups were defined based on a patient’s maximum weight loss, those with longer follow-up time are inherently more likely to be classified as a super-responder. This is reflected in the fact that super-responders had twice the average follow-up of non-responders. Third, given the short follow-up duration, the primary exposure studied is low-dose oral semaglutide during titration rather than maintenance dosing. Fourth, the analyses could be impacted by missing data, which is an expected but important shortcoming of retrospectively analyzing data collected in routine clinical care contexts. For example, only 36% of patients with an index weight had a follow-up weight in the defined observation window, and those who returned for a weight may differ systematically from those who did not. Fifth, the pre-index weights are clinical weights taken for other reasons at irregular intervals, and not all patients had prior weights dating back five years before treatment initiation. Sixth, the prescription records used to define the cohorts here do not establish medication adherence, and it is likely that some patients with prescriptions never started the medication or did not take it as directed. Additional analyses to characterize adherence across the response groups would strengthen the analysis. Finally, the orforglipron cohort is small with very limited follow-up. The data presented for this cohort is descriptive and is not directly comparable with the oral semaglutide cohort.
These findings suggestthat in GLP-1 RA naive patients, the early response to oral Wegovy is characterized by the trajectory of the patient's weight over the preceding years rather than by age, sex, or standard glycemic or hemodynamic measurements. Strikingly, within months of treatment initiation, the average weight of the super-responder subset returned to their average weight from five years earlier. The findings motivate prospective evaluation of pre-treatment weight trajectory as a possible predictor of response and a re-examination of this cohort after additional follow-up has accrued and maintenance-dose exposure has further occurred.
Supplementary Materials
The following supporting information can be downloaded at the website of this paper posted on Preprints.org.
Author Contributions
Venky Soundararajan conceived and supervised the study. Venky Soundararajan and Karthik Murugadoss designed the study. Karthik Murugadoss performed the analyses and prepared the visualizations with A.J. Venkatakrishnan. All authors prepared, reviewed, and approved the final manuscript.
Funding
No external funding was received for this study.
Data Availability Statement
This study analyzed de-identified electronic health record data. The data were extracted under an established privacy-preserving protocol and cannot be shared beyond what is reported here due to the parameters of the expert determination.
Code Availability
The analysis code is not publicly available. Please contact the corresponding author for details.
Acknowledgments
The authors thank Patrick Lenehan for thorough review of the manuscript.
Conflicts of Interest
The authors are employees of nference, inc., which conducts research collaborations with various biopharmaceutical companies whose therapeutic products are included in this study. None of these companies, nor any other nference collaborator, funded, supported, or had any role in the independent study design, data acquisition, analysis, interpretation, manuscript preparation, or the decision to submit this work for publication. All analyses were conducted by the authors using de-identified electronic health record data. The authors declare no additional competing interests.
References
- NCD Risk Factor Collaboration (NCD-RisC). Worldwide trends in underweight and obesity from 1990 to 2022: a pooled analysis of 3663 population-representative studies with 222 million children, adolescents, and adults. Lancet 2024, 403, 1027–1050. [Google Scholar] [CrossRef] [PubMed]
- Wilding, J. P. H.; et al. Once-weekly semaglutide in adults with overweight or obesity. N. Engl. J. Med. 2021, 384, 989–1002. [Google Scholar] [CrossRef] [PubMed]
- Jastreboff, A. M.; et al. Tirzepatide once weekly for the treatment of obesity. N. Engl. J. Med. 2022, 387, 205–216. [Google Scholar] [CrossRef] [PubMed]
- Wharton, S.; et al. Oral semaglutide at a dose of 25 mg in adults with overweight or obesity. N. Engl. J. Med. 2025, 393, 1077–1087. [Google Scholar] [CrossRef] [PubMed]
- Williamson, D. A.; Bray, G. A.; Ryan, D. H. Is 5% weight loss a satisfactory criterion to define clinically significant weight loss? Obesity 2015, 23, 2319–2320. [Google Scholar] [CrossRef] [PubMed]
- Jensen, M. D.; et al. Reprint: 2013 AHA/ACC/TOS guideline for the management of overweight and obesity in adults. J. Am. Pharm. Assoc. 2003, 129, e3. [Google Scholar]
- Wing, R. R.; et al. Benefits of modest weight loss in improving cardiovascular risk factors in overweight and obese individuals with type 2 diabetes. Diabetes Care 2011, 34, 1481–1486. [Google Scholar] [CrossRef] [PubMed]
- Garvey, W. T.; et al. American Association of Clinical Endocrinologists and American College of Endocrinology comprehensive clinical practice guidelines for medical care of patients with obesity. Endocr. Pract. 2016, 22 Suppl 3, 1–203. [Google Scholar] [CrossRef] [PubMed]
- Davies, M.; et al. Semaglutide 2·4 mg once a week in adults with overweight or obesity, and type 2 diabetes (STEP 2): a randomised, double-blind, double-dummy, placebo-controlled, phase 3 trial. Lancet 2021, 397, 971–984. [Google Scholar] [CrossRef] [PubMed]
- Hong, B.; Kim, H.; Lee, D.; Kim, K. Weight loss effects of once-weekly semaglutide 2.4 mg in adults with and without type 2 diabetes: A systematic review and meta-analysis. Pharmaceuticals 2025, 18, 1058. [Google Scholar] [CrossRef] [PubMed]
- Yang, Y.; et al. Sex differences in the efficacy of glucagon-like peptide-1 receptor agonists for weight reduction: A systematic review and meta-analysis. J. Diabetes 2025, 17, e70063. [Google Scholar] [CrossRef] [PubMed]
- Ard, J.; et al. Weight reduction over time in tirzepatide-treated participants by early weight loss response: Post hoc analysis in SURMOUNT-1. Diabetes Obes. Metab. 2025, 27, 5064–5071. [Google Scholar] [CrossRef] [PubMed]
- Fujioka, K.; et al. Early weight loss with liraglutide 3.0 mg predicts 1-year weight loss and is associated with improvements in clinical markers. Obesity 2016, 24, 2278–2288. [Google Scholar] [CrossRef] [PubMed]
- Ghusn, W.; et al. Weight loss outcomes associated with semaglutide treatment for patients with overweight or obesity. JAMA Netw. Open 2022, 5, e2231982. [Google Scholar] [CrossRef] [PubMed]
- Gasoyan, H.; et al. One-year weight reduction with semaglutide or liraglutide in clinical practice. JAMA Netw. Open 2024, 7, e2433326. [Google Scholar] [CrossRef] [PubMed]
- Acosta, A.; et al. Selection of antiobesity medications based on phenotypes enhances weight loss: A pragmatic trial in an obesity clinic. Obesity 2021, 29, 662–671. [Google Scholar] [CrossRef] [PubMed]
- Venkatakrishnan, A. J.; Murugadoss, K.; Soundararajan, V. Decoding the hallmarks of GLP-1RA weight-loss super-responders. Biol. Methods Protoc. 2026, 11. [Google Scholar] [CrossRef] [PubMed]
- Wharton, S.; et al. Orforglipron, an oral small-molecule GLP-1 receptor agonist for obesity treatment. N. Engl. J. Med. 2025, 393, 1796–1806. [Google Scholar] [CrossRef] [PubMed]
- Rodriguez, P. J.; et al. Semaglutide vs tirzepatide for weight loss in adults with overweight or obesity. JAMA Intern. Med. 2024, 184, 1056–1064. [Google Scholar] [CrossRef] [PubMed]
- Wagner, T.; et al. Augmented curation of clinical notes from a massive EHR system reveals symptoms of impending COVID-19 diagnosis. Elife 2020, 9, e58227. [Google Scholar] [CrossRef] [PubMed]
- Murugadoss, K.; Venkatakrishnan, A. J.; Soundararajan, V. GLP-1-based incretin therapy is associated with lower incident Alzheimer’s disease and cardiorenal events in adults with documented neuropsychiatric, cognitive, or sensory risk. Biol. Methods Protoc. 2026, 11, bpag043. [Google Scholar] [CrossRef] [PubMed]
- Varma, G.; et al. Auditable large language model curation of clinical notes refines glucagon-like peptide-1 initiation, persistence ascertainment, and compounding use beyond prescription records. Biol. Methods Protoc. 2026, 11, bpag035. [Google Scholar] [CrossRef] [PubMed]
- Venkatakrishnan, A. J.; Murugadoss, K.; Soundararajan, V. Weight-loss dynamics with tirzepatide versus semaglutide. PNAS Nexus 2026, 5, pgag171. [Google Scholar] [CrossRef] [PubMed]
- Murugadoss, K.; Venkatakrishnan, A. J.; Soundararajan, V. Comparison of cardiometabolic benefits and tolerability in patients on sustained low doses of semaglutide or tirzepatide. Biol. Methods Protoc. 2026, bpag048. [Google Scholar] [CrossRef] [PubMed]
- von Elm, E.; et al. The Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement: guidelines for reporting observational studies. PLoS Med. 2007, 4, e296. [Google Scholar] [CrossRef] [PubMed]
- Benchimol, E. I.; et al. The REporting of studies Conducted using Observational Routinely-collected health Data (RECORD) statement. PLoS Med. 2015, 12, e1001885. [Google Scholar] [CrossRef] [PubMed]
- Lund, J. L.; Richardson, D. B.; Stürmer, T. The active comparator, new user study design in pharmacoepidemiology: historical foundations and contemporary application. Curr. Epidemiol. Rep. 2015, 2, 221–228. [Google Scholar] [CrossRef] [PubMed]
- Murugadoss, K.; et al. Building a best-in-class automated de-identification tool for electronic health records through ensemble learning. Patterns (N. Y.) 2021, 2, 100255. [Google Scholar] [CrossRef] [PubMed]
- Murugadoss, K.; et al. Scaling text de-identification using locally augmented ensembles. medRxiv 2024. [Google Scholar] [CrossRef]
- Barnett, A. G.; van der Pols, J. C.; Dobson, A. J. Regression to the mean: what it is and how to deal with it. Int. J. Epidemiol. 2005, 34, 215–220. [Google Scholar] [CrossRef] [PubMed]
- Tronieri, J. S.; et al. ‘last supper’ predicts greater weight loss early in obesity treatment, but not enough to offset initial gains. Front. Psychol. 2018, 9, 1335. [Google Scholar] [CrossRef] [PubMed]
- Jacobs, A.; et al. Preoperative weight gain is not related to lower postoperative weight loss, but to lower total weight loss up to 3 years after bariatric-metabolic surgery. Obes. Surg. 2023, 33, 3746–3754. [Google Scholar] [CrossRef] [PubMed]
- Wong, H. J.; et al. Efficacy of GLP-1 receptor agonists on weight loss, BMI, and waist circumference for patients with obesity or overweight: A systematic review, meta-analysis, and meta-regression of 47 randomized Controlled Trials. Diabetes Care 2025, 48, 292–300. [Google Scholar] [CrossRef] [PubMed]
- Neter, J. E.; Stam, B. E.; Kok, F. J.; Grobbee, D. E.; Geleijnse, J. M. Influence of weight reduction on blood pressure: a meta-analysis of randomized controlled trials. Hypertension 2003, 42, 878–884. [Google Scholar] [PubMed]
Figure 2.
Weight change among GLP-1 RA naive oral Wegovy initiators. (A) Mean percent change from the index weight from two years before to 240 days after the first prescription (N=8,381 with an index weight); the pre-index axis is compressed, the number of patients contributing is shown below each tick, and the day-210 mean is the average of the day-180 and day-240 means as described in Methods. (B) Share of patients with a weight at each timepoint whose change had reached 2.5%, 5%, 10%, 15% or 20% loss, at days 30, 60, 90 and 180, with the number evaluated at each day in the legend. Bars and labels resting on fewer than 11 patients are drawn but labeled <11.
Figure 2.
Weight change among GLP-1 RA naive oral Wegovy initiators. (A) Mean percent change from the index weight from two years before to 240 days after the first prescription (N=8,381 with an index weight); the pre-index axis is compressed, the number of patients contributing is shown below each tick, and the day-210 mean is the average of the day-180 and day-240 means as described in Methods. (B) Share of patients with a weight at each timepoint whose change had reached 2.5%, 5%, 10%, 15% or 20% loss, at days 30, 60, 90 and 180, with the number evaluated at each day in the legend. Bars and labels resting on fewer than 11 patients are drawn but labeled <11.
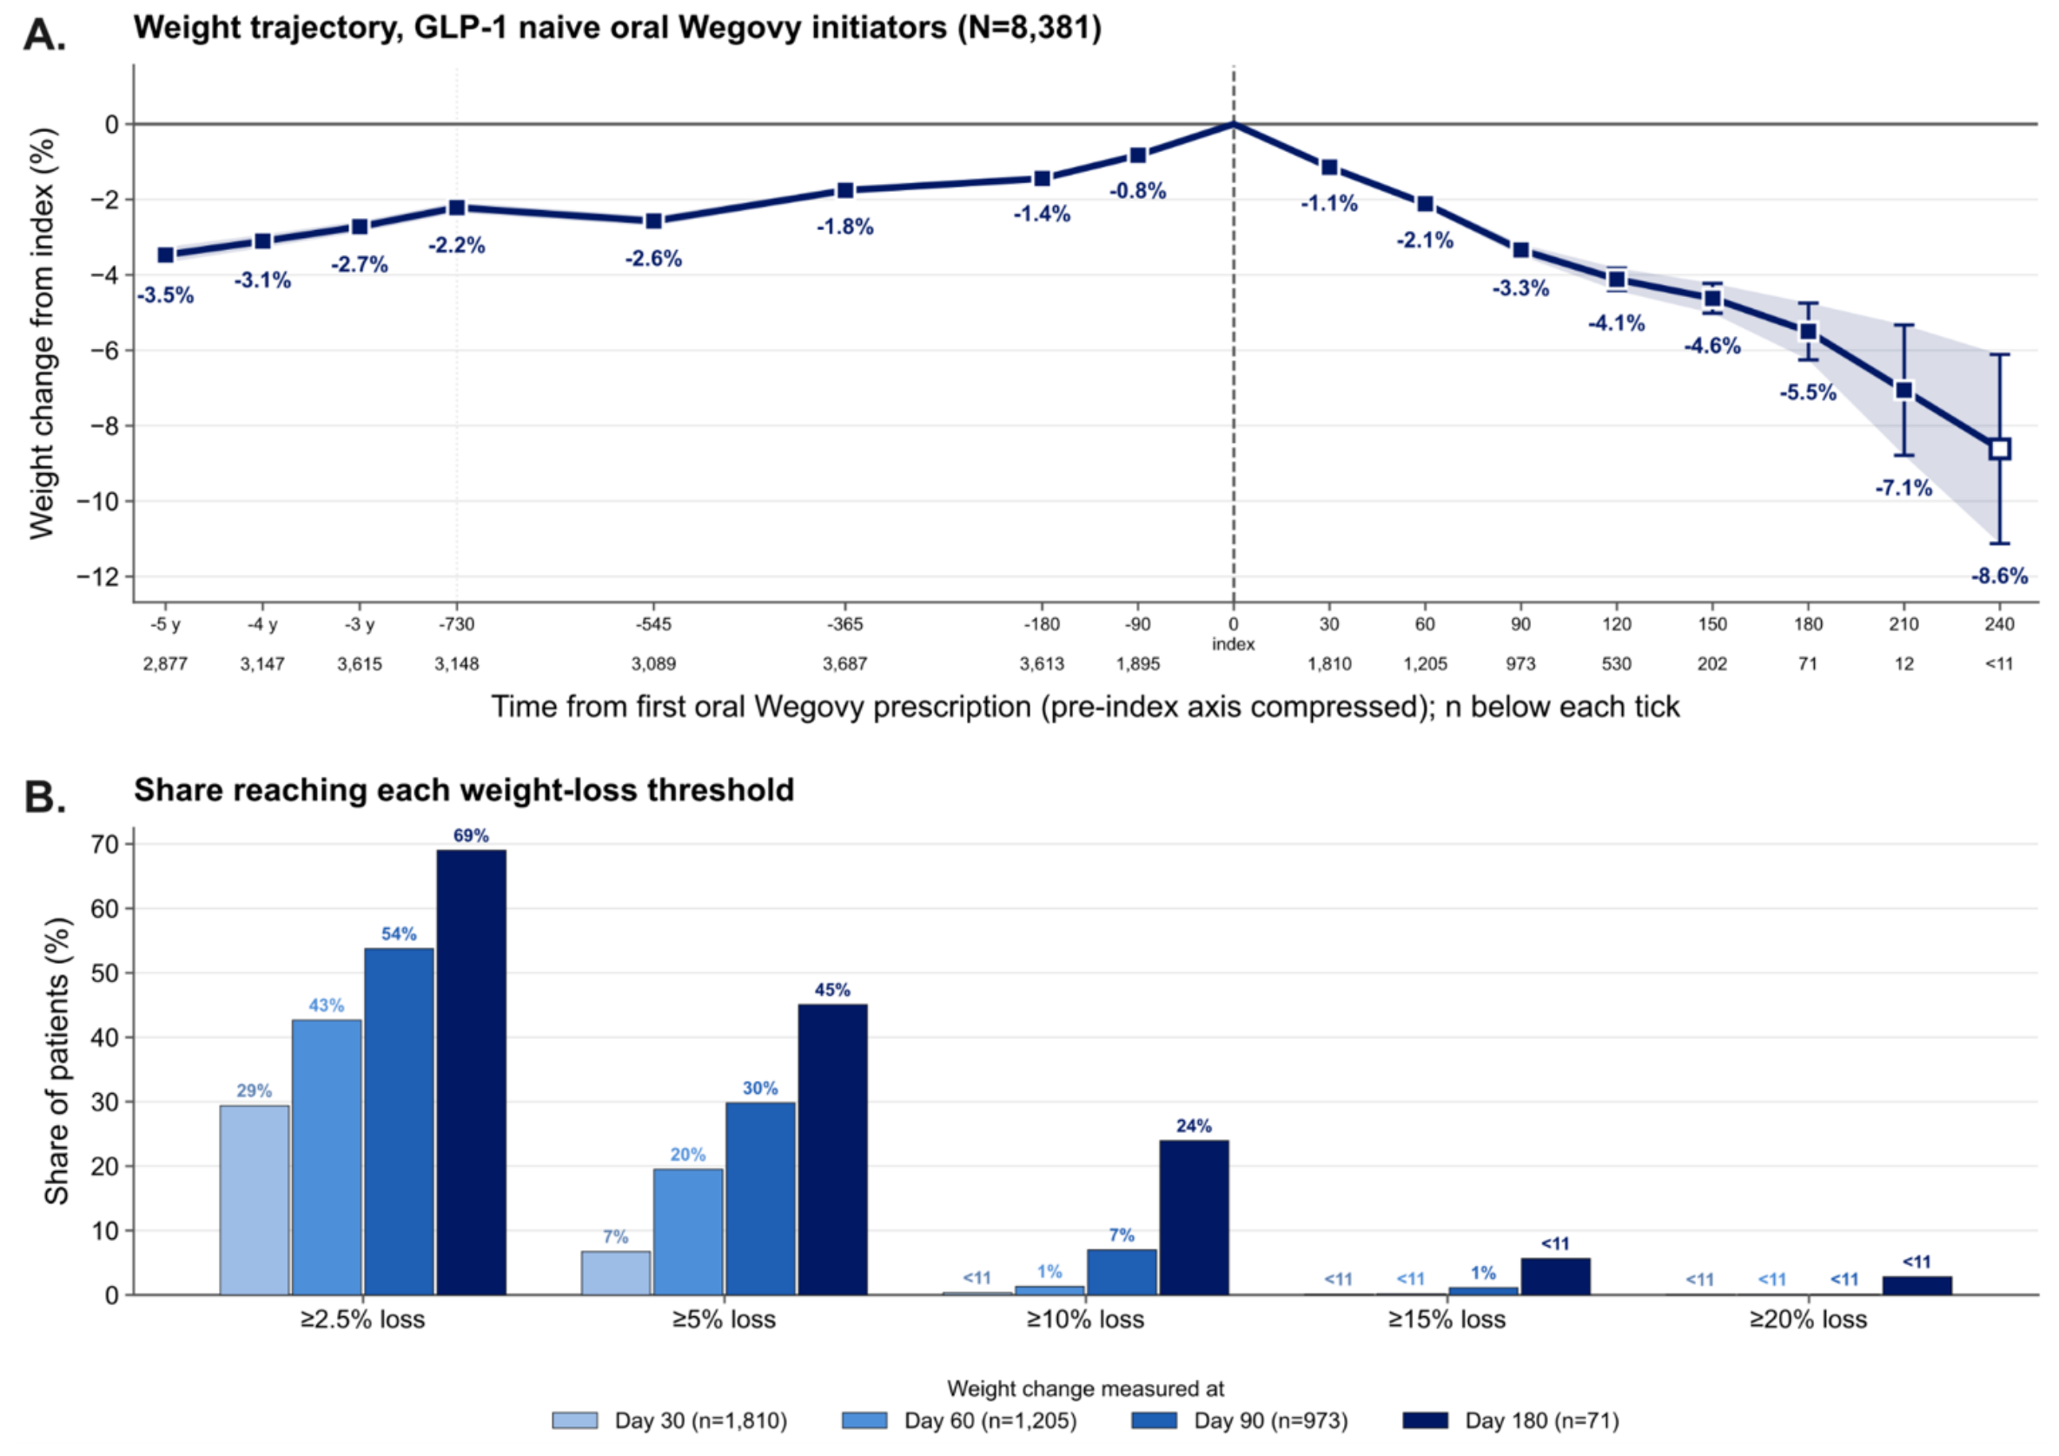
Figure 4.
Within-patient change in (A) HbA1c, (B) systolic and (C) diastolic blood pressure by responder group, from five years before to 90 days (HbA1c) or 180 days (blood pressure) after the first oral Wegovy prescription. Each point is the mean change from the patient's index value among group members with a reading in that window. The legend below each panel gives the number of patients in each group with an index value and the mean index value; 2,431 patients had an index HbA1c and 6,536 an index blood pressure. HbA1c after the index date rests on fewer than 11 patients per group at every timepoint. Points resting on fewer than 11 patients are drawn as open markers.
Figure 4.
Within-patient change in (A) HbA1c, (B) systolic and (C) diastolic blood pressure by responder group, from five years before to 90 days (HbA1c) or 180 days (blood pressure) after the first oral Wegovy prescription. Each point is the mean change from the patient's index value among group members with a reading in that window. The legend below each panel gives the number of patients in each group with an index value and the mean index value; 2,431 patients had an index HbA1c and 6,536 an index blood pressure. HbA1c after the index date rests on fewer than 11 patients per group at every timepoint. Points resting on fewer than 11 patients are drawn as open markers.
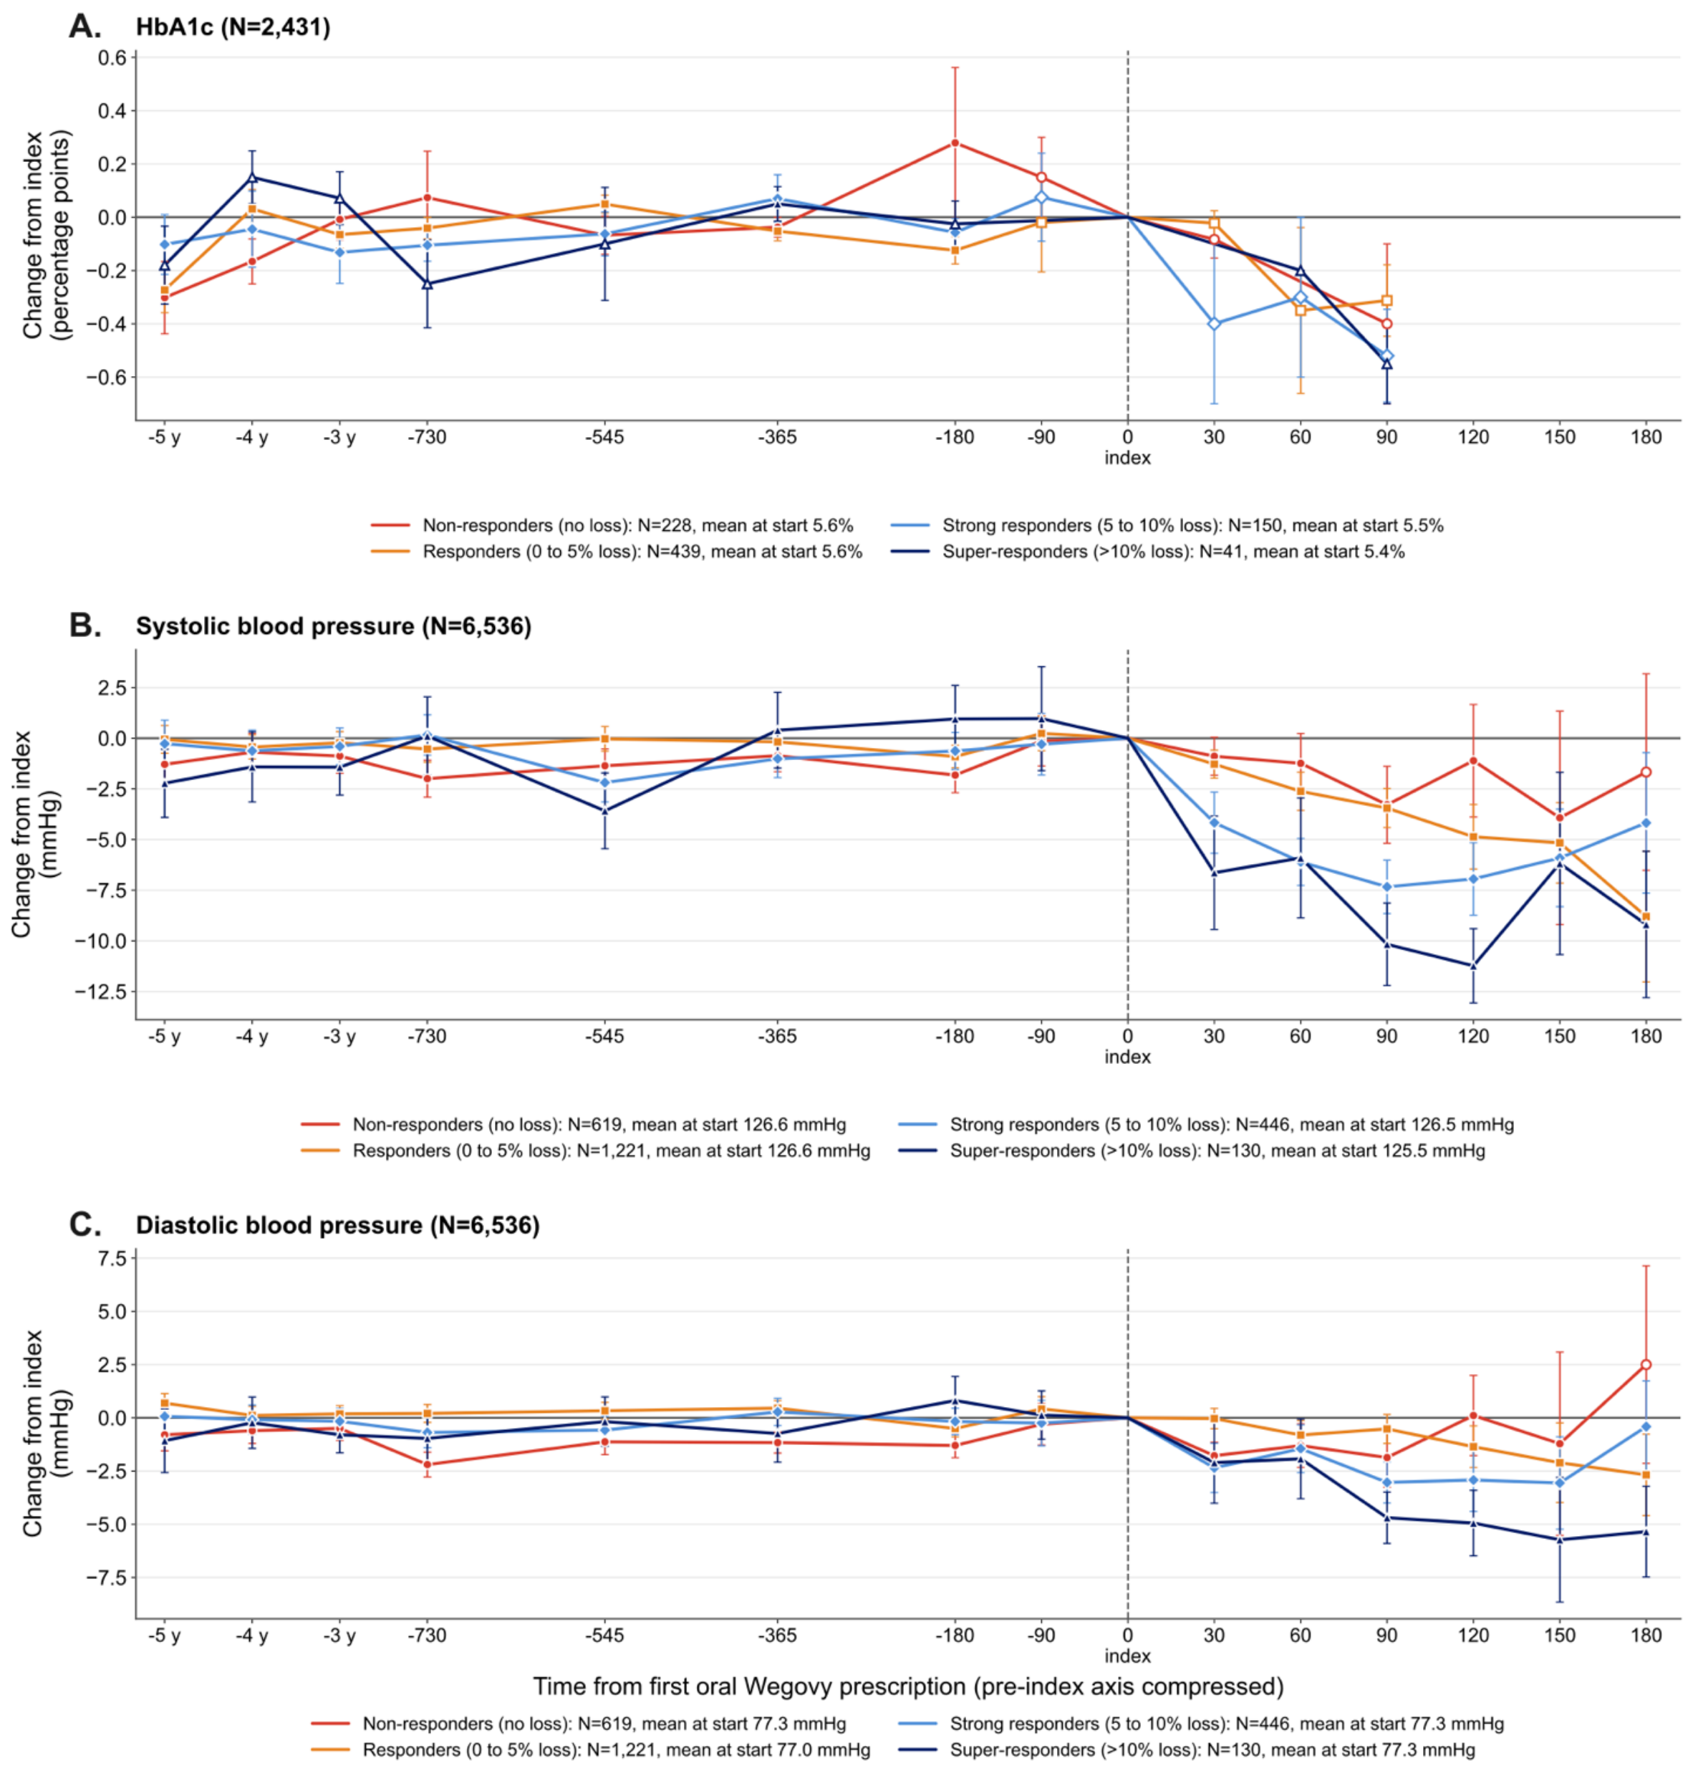
Figure 5.
Early weight change among GLP-1 RA naive orforglipron (Foundayo) initiators. (A) Mean percent change from the index weight (N=332 with an index weight), with the number of patients below each tick. (B) Distribution of the best percent change within 180 days (N=54), colored by responder group. (C) Share reaching each weight-loss threshold at days 30, 60 and 90. Follow-up extends to about 60 days for most patients, so the best change is the best of few readings and is not comparable to Figure 2B. Orange denotes orforglipron in panel A; responder-group colors follow Figure 1. Bars and points resting on fewer than 11 patients are drawn but labeled <11 or as open markers. (D) Weight trajectories of the orforglipron (Foundayo) responder groups, in the layout of Figure 3 (N=54; 19 non-responders, 33 responders, <11 strong responders, no super-responders). Most pre-index points rest on fewer than 11 patients and are drawn as open markers; no statistical comparison was made.
Figure 5.
Early weight change among GLP-1 RA naive orforglipron (Foundayo) initiators. (A) Mean percent change from the index weight (N=332 with an index weight), with the number of patients below each tick. (B) Distribution of the best percent change within 180 days (N=54), colored by responder group. (C) Share reaching each weight-loss threshold at days 30, 60 and 90. Follow-up extends to about 60 days for most patients, so the best change is the best of few readings and is not comparable to Figure 2B. Orange denotes orforglipron in panel A; responder-group colors follow Figure 1. Bars and points resting on fewer than 11 patients are drawn but labeled <11 or as open markers. (D) Weight trajectories of the orforglipron (Foundayo) responder groups, in the layout of Figure 3 (N=54; 19 non-responders, 33 responders, <11 strong responders, no super-responders). Most pre-index points rest on fewer than 11 patients and are drawn as open markers; no statistical comparison was made.
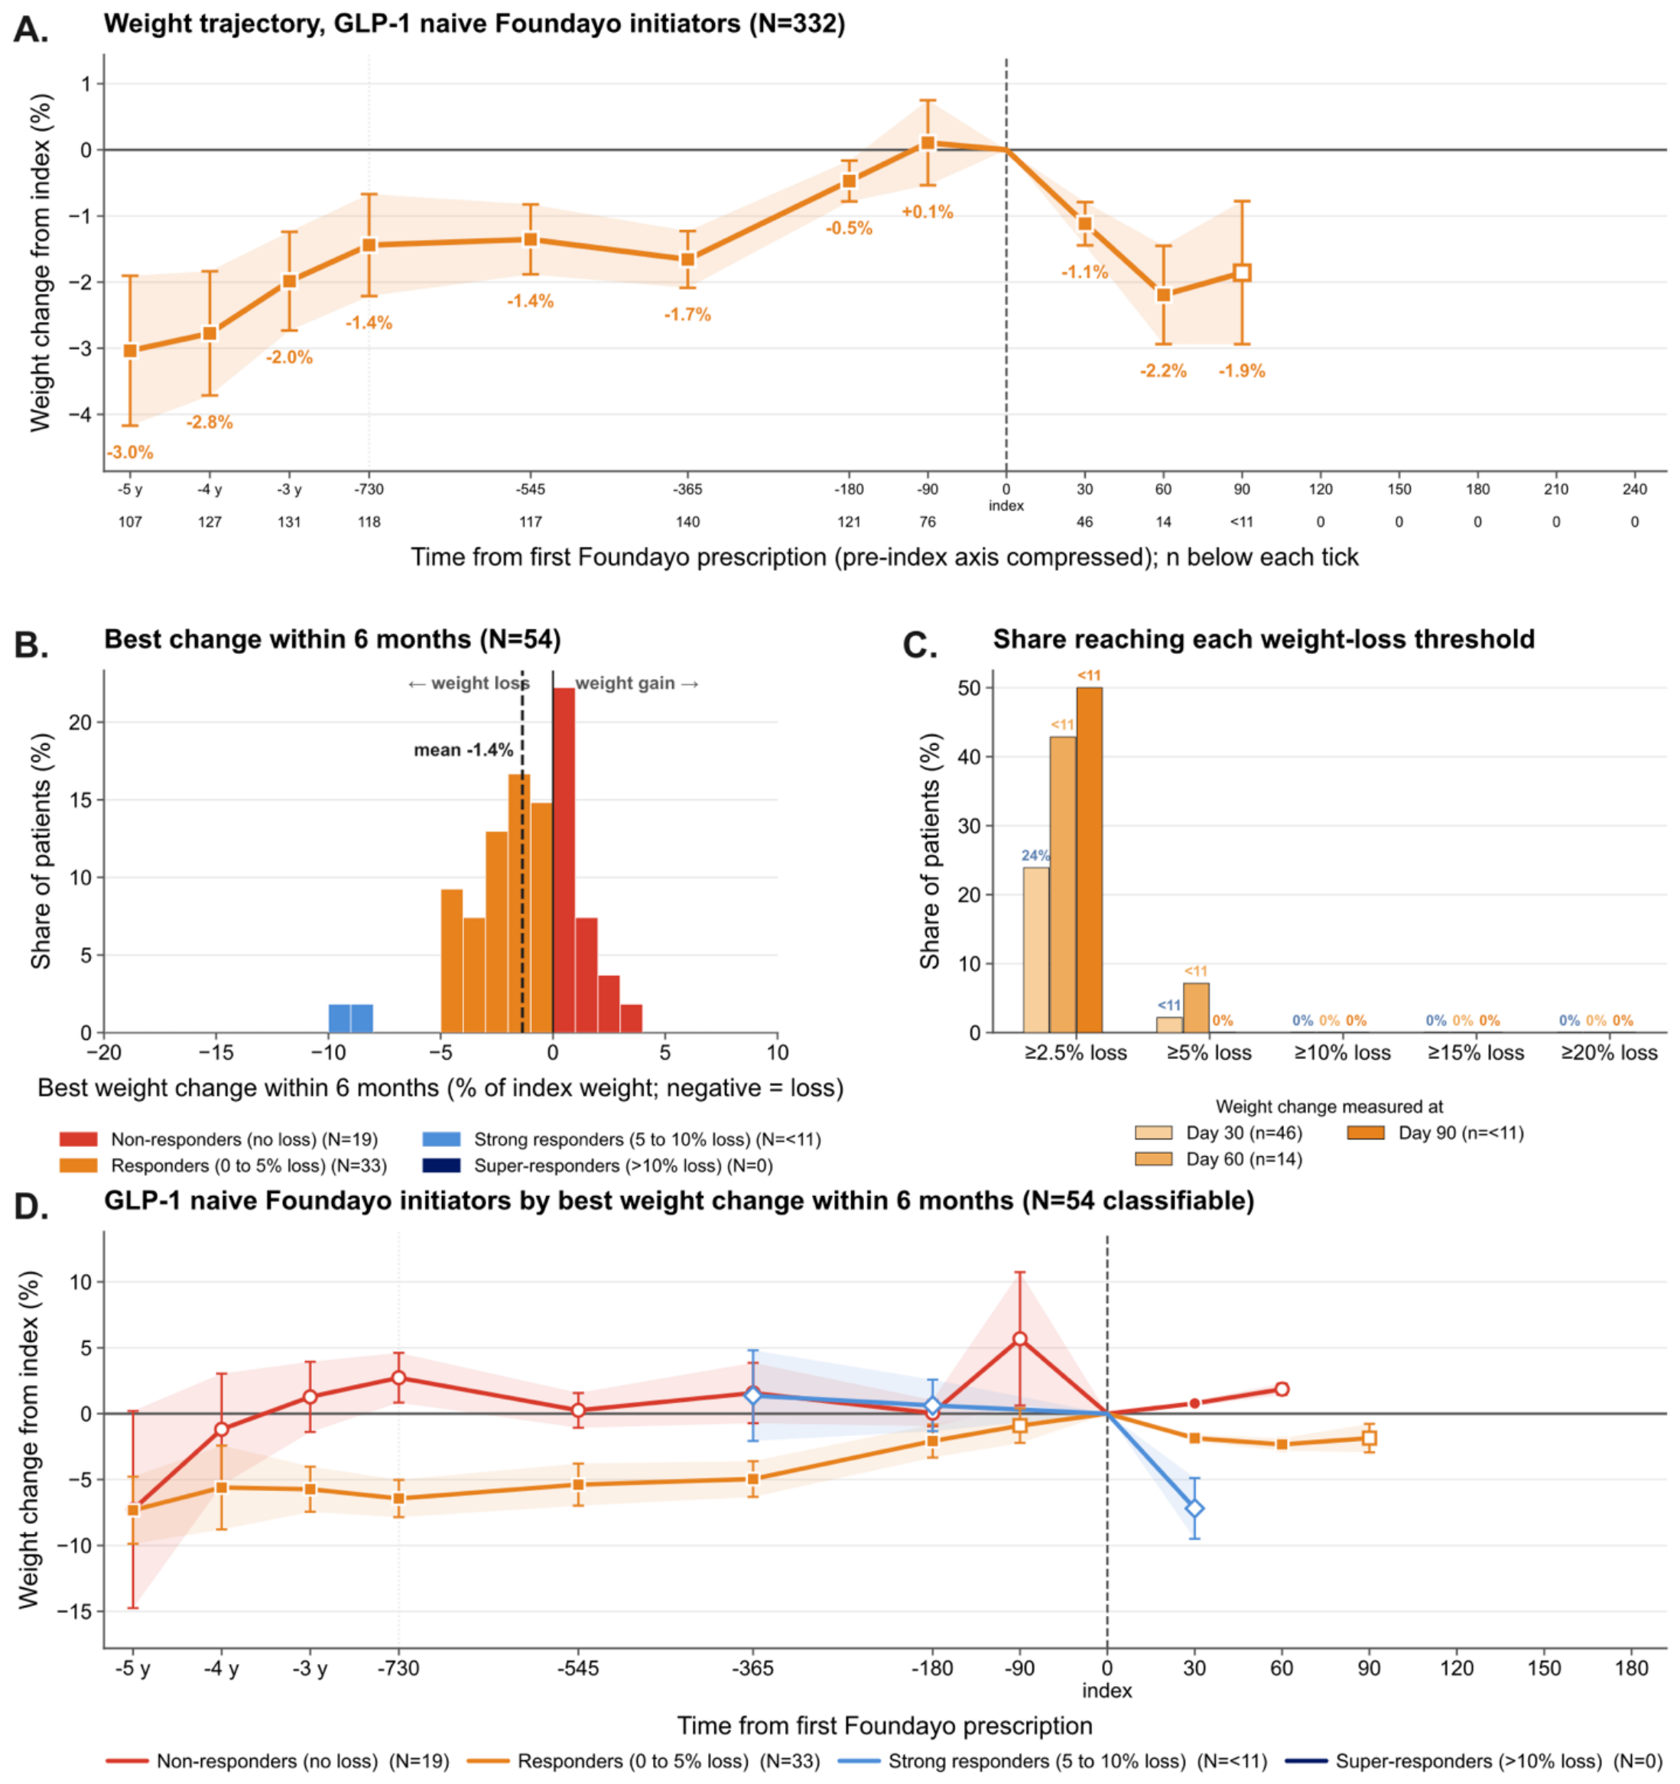

Table 1.
Characteristics of GLP-1 RA naive oral Wegovy initiators by responder group. The four groups are defined by the best percent weight change within 180 days of the first prescription (N=3,011); membership was assigned once and held fixed. Continuous variables are mean (SD); categorical variables are count (column percentage). Where a measure was available for fewer patients than the group holds, the number contributing is given in the cell. Weight one, two and five years before the index date is the median reading in a window around that timepoint, shown in kilograms and as a percent of the index weight, so a negative percent means the patient weighed less then than at the start of treatment. HbA1c and blood pressure are levels. Comorbidities are any qualifying diagnosis code on or before the index date. Prescribed dose at day 60 is the strength of the last prescription written on or before day 60, among patients whose record extended past day 60, with that number shown per group. P values are from one-way ANOVA (continuous) or the chi-square test (categorical), and P trend is a linear contrast across the four groups in order; both are unadjusted. Cells with counts <11 are reported as <11 per the privacy convention adopted in this study (Figure 1, Figure 3).
Table 1.
Characteristics of GLP-1 RA naive oral Wegovy initiators by responder group. The four groups are defined by the best percent weight change within 180 days of the first prescription (N=3,011); membership was assigned once and held fixed. Continuous variables are mean (SD); categorical variables are count (column percentage). Where a measure was available for fewer patients than the group holds, the number contributing is given in the cell. Weight one, two and five years before the index date is the median reading in a window around that timepoint, shown in kilograms and as a percent of the index weight, so a negative percent means the patient weighed less then than at the start of treatment. HbA1c and blood pressure are levels. Comorbidities are any qualifying diagnosis code on or before the index date. Prescribed dose at day 60 is the strength of the last prescription written on or before day 60, among patients whose record extended past day 60, with that number shown per group. P values are from one-way ANOVA (continuous) or the chi-square test (categorical), and P trend is a linear contrast across the four groups in order; both are unadjusted. Cells with counts <11 are reported as <11 per the privacy convention adopted in this study (Figure 1, Figure 3).
| Characteristic | Non-responders (no loss) (N=750) | Responders (0 to 5% loss) (N=1,547) | Strong responders (5 to 10% loss) (N=549) | Super-responders (>10% loss) (N=165) | P (ANOVA / chi-square) | P trend |
|---|---|---|---|---|---|---|
| Demographics | ||||||
| Age, years | 53.3 (16.3), n=735 | 54.5 (15.4), n=1,528 | 53.8 (14.9), n=547 | 51.5 (15.1), n=164 | 0.065 | 0.138 |
| Female | 534 (71.2%) | 1,152 (74.5%) | 422 (76.9%) | 123 (74.5%) | 0.133 | |
| Race: White | 560 (74.7%) | 1,169 (75.6%) | 434 (79.1%) | 138 (83.6%) | 0.032 | |
| Race: Black or African American | 117 (15.6%) | 237 (15.3%) | 66 (12.0%) | 17 (10.3%) | 0.085 | |
| Race: Asian | 13 (1.7%) | 26 (1.7%) | <11 (1.8%) | <11 (2.4%) | 0.921 | |
| Race: Other | 15 (2.0%) | 18 (1.2%) | <11 (0.4%) | 0 (0.0%) | 0.023 | |
| Race: Unknown | 45 (6.0%) | 97 (6.3%) | 37 (6.7%) | <11 (3.6%) | 0.531 | |
| Weight | ||||||
| Weight at index, kg | 101.7 (24.5) | 98.3 (21.6) | 95.9 (20.5) | 94.1 (20.2) | <0.001 | <0.001 |
| Body mass index at index | 34.9 (5.3), n=721 | 34.1 (5.0), n=1,497 | 33.5 (4.8), n=527 | 33.0 (4.5), n=160 | <0.001 | <0.001 |
| Weight 1 year before index, kg | 99.3 (22.9), n=349 | 95.2 (20.8), n=797 | 92.1 (19.5), n=271 | 89.8 (20.4), n=85 | <0.001 | <0.001 |
| Weight 2 years before index, kg | 96.8 (21.7), n=292 | 94.0 (20.5), n=708 | 92.0 (20.5), n=251 | 87.2 (21.2), n=64 | 0.003 | <0.001 |
| Weight 5 years before index, kg | 95.0 (20.7), n=254 | 91.8 (21.7), n=621 | 90.3 (21.2), n=230 | 85.1 (20.6), n=64 | 0.004 | <0.001 |
| Weight 1 year before, % of index | -0.7 (6.8), n=349 | -1.7 (6.0), n=797 | -2.1 (5.6), n=271 | -3.4 (5.2), n=85 | 0.001 | <0.001 |
| Weight 2 years before, % of index | -1.4 (9.1), n=292 | -2.4 (7.8), n=708 | -2.9 (7.8), n=251 | -5.1 (7.5), n=64 | 0.007 | <0.001 |
| Weight 5 years before, % of index | -0.8 (13.6), n=254 | -4.0 (11.1), n=621 | -4.1 (9.7), n=230 | -7.6 (11.8), n=64 | <0.001 | <0.001 |
| Days from index to latest weight | 60.5 (39.8) | 67.1 (45.4) | 99.2 (67.0) | 125.4 (67.9) | <0.001 | <0.001 |
| Best weight change within 6 months, % | 1.6 (4.1) | -2.3 (1.4) | -7.1 (1.4) | -13.6 (5.3) | <0.001 | <0.001 |
| HbA1c | ||||||
| HbA1c at index, % | 5.6 (0.6), n=228 | 5.6 (0.7), n=439 | 5.5 (0.5), n=150 | 5.4 (0.6), n=41 | 0.160 | 0.054 |
| HbA1c 1 year before, % | 5.6 (0.6), n=65 | 5.6 (0.7), n=148 | 5.6 (0.6), n=44 | 5.5 (0.5), n=17 | 0.905 | 0.539 |
| HbA1c 2 years before, % | 5.5 (0.9), n=64 | 5.5 (0.6), n=95 | 5.5 (0.4), n=36 | 5.4 (0.4), n=<11 | 0.902 | 0.486 |
| HbA1c 5 years before, % | 5.7 (0.7), n=53 | 5.7 (0.6), n=81 | 5.8 (0.8), n=32 | 5.6 (0.6), n=11 | 0.733 | 0.695 |
| Blood pressure | ||||||
| Systolic BP at index, mmHg | 126.6 (15.1), n=619 | 126.6 (14.0), n=1,221 | 126.5 (14.4), n=446 | 125.5 (13.1), n=130 | 0.858 | 0.414 |
| Systolic BP 1 year before, mmHg | 125.0 (12.7), n=408 | 125.8 (13.7), n=862 | 123.8 (13.7), n=301 | 125.4 (13.7), n=90 | 0.175 | 0.862 |
| Systolic BP 2 years before, mmHg | 124.7 (14.4), n=339 | 126.0 (13.7), n=752 | 124.4 (12.1), n=265 | 123.3 (11.3), n=72 | 0.147 | 0.275 |
| Systolic BP 5 years before, mmHg | 125.2 (14.5), n=285 | 125.7 (13.6), n=666 | 124.6 (14.2), n=246 | 123.4 (13.0), n=71 | 0.474 | 0.255 |
| Diastolic BP at index, mmHg | 77.3 (9.8), n=619 | 77.0 (9.8), n=1,221 | 77.3 (9.9), n=446 | 77.3 (9.2), n=130 | 0.856 | 0.896 |
| Diastolic BP 1 year before, mmHg | 76.5 (8.1), n=409 | 76.8 (9.1), n=864 | 76.7 (9.2), n=301 | 77.5 (9.7), n=90 | 0.834 | 0.371 |
| Diastolic BP 2 years before, mmHg | 75.7 (9.6), n=339 | 76.8 (8.8), n=752 | 75.5 (9.1), n=265 | 75.4 (7.2), n=72 | 0.118 | 0.536 |
| Diastolic BP 5 years before, mmHg | 76.5 (9.5), n=285 | 76.8 (8.9), n=666 | 75.9 (8.4), n=246 | 76.0 (10.0), n=71 | 0.532 | 0.509 |
| Comorbidities | ||||||
| Type 2 diabetes | 59 (7.9%) | 100 (6.5%) | 27 (4.9%) | <11 (5.5%) | 0.181 | |
| Hypertension | 353 (47.1%) | 758 (49.0%) | 234 (42.6%) | 72 (43.6%) | 0.059 | |
| Hyperlipidemia | 402 (53.6%) | 817 (52.8%) | 294 (53.6%) | 74 (44.8%) | 0.213 | |
| Coronary artery disease | 93 (12.4%) | 183 (11.8%) | 60 (10.9%) | 20 (12.1%) | 0.879 | |
| Heart failure | 50 (6.7%) | 63 (4.1%) | 20 (3.6%) | <11 (5.5%) | 0.025 | |
| Stroke or TIA | 47 (6.3%) | 97 (6.3%) | 31 (5.6%) | <11 (6.1%) | 0.960 | |
| Prediabetes | 274 (36.5%) | 575 (37.2%) | 178 (32.4%) | 43 (26.1%) | 0.012 | |
| Hypothyroidism | 133 (17.7%) | 231 (14.9%) | 83 (15.1%) | 20 (12.1%) | 0.192 | |
| Polycystic ovary syndrome | 42 (5.6%) | 56 (3.6%) | 12 (2.2%) | <11 (5.5%) | 0.010 | |
| Chronic kidney disease | 70 (9.3%) | 129 (8.3%) | 37 (6.7%) | 15 (9.1%) | 0.402 | |
| Gastroesophageal reflux disease | 246 (32.8%) | 530 (34.3%) | 172 (31.3%) | 44 (26.7%) | 0.186 | |
| Gallbladder disease | 54 (7.2%) | 103 (6.7%) | 27 (4.9%) | <11 (6.1%) | 0.393 | |
| Pancreatitis | 11 (1.5%) | <11 (0.5%) | <11 (0.7%) | <11 (1.8%) | 0.065 | |
| Substance use disorder | 67 (8.9%) | 96 (6.2%) | 34 (6.2%) | 14 (8.5%) | 0.075 | |
| Depression | 239 (31.9%) | 430 (27.8%) | 171 (31.1%) | 47 (28.5%) | 0.173 | |
| Anxiety disorder | 313 (41.7%) | 623 (40.3%) | 222 (40.4%) | 71 (43.0%) | 0.845 | |
| Obstructive sleep apnea | 210 (28.0%) | 358 (23.1%) | 120 (21.9%) | 26 (15.8%) | 0.002 | |
| Osteoarthritis | 236 (31.5%) | 478 (30.9%) | 155 (28.2%) | 46 (27.9%) | 0.513 | |
| Tobacco use disorder | 109 (14.5%) | 172 (11.1%) | 54 (9.8%) | <11 (4.8%) | 0.001 | |
| Malignancy (excluding non-melanoma skin) | 104 (13.9%) | 247 (16.0%) | 68 (12.4%) | 23 (13.9%) | 0.186 | |
| Venous thromboembolism | 37 (4.9%) | 61 (3.9%) | 19 (3.5%) | <11 (3.6%) | 0.554 | |
| Medications prescribed in the year before index | ||||||
| Metformin | 86 (11.5%) | 187 (12.1%) | 52 (9.5%) | 18 (10.9%) | 0.425 | |
| SGLT2 inhibitor | 22 (2.9%) | 43 (2.8%) | <11 (1.6%) | <11 (3.0%) | 0.454 | |
| ACE inhibitor or ARB | 221 (29.5%) | 442 (28.6%) | 158 (28.8%) | 47 (28.5%) | 0.976 | |
| Beta blocker | 165 (22.0%) | 334 (21.6%) | 99 (18.0%) | 33 (20.0%) | 0.285 | |
| Calcium-channel blocker | 130 (17.3%) | 272 (17.6%) | 75 (13.7%) | 19 (11.5%) | 0.048 | |
| Diuretic | 177 (23.6%) | 357 (23.1%) | 122 (22.2%) | 31 (18.8%) | 0.582 | |
| Prescribed dose at day 60, among patients observed past day 60 | ||||||
| Observed past day 60 with a prescribed dose | 424 (56.5%) | 935 (60.4%) | 460 (83.8%) | 160 (97.0%) | ||
| 1.5 mg | 257 (60.6%) | 511 (54.7%) | 223 (48.5%) | 67 (41.9%) | <0.001 | |
| 4 mg | 126 (29.7%) | 336 (35.9%) | 178 (38.7%) | 68 (42.5%) | 0.009 | |
| 9 or 25 mg | 41 (9.7%) | 88 (9.4%) | 59 (12.8%) | 25 (15.6%) | 0.041 | |
Table 2.
Phenotypes extracted from clinical notes before treatment, by responder group. The four groups are the GLP-1 RA naive oral Wegovy initiators of Table 1 (N=3,011), classified by the best percent weight change within 180 days of the first prescription. A phenotype is present when the note-curation model recorded at least one affirmative mention of it (probability at or above 0.8) in a note dated on or before the index date, anywhere in the patient's available record with no look-back limit, the same pre-index window used for the comorbidities in Table 1. Cells are count (column percentage). The first P is from the chi-square test across the four groups and the second from Fisher's exact test comparing non-responders with super-responders alone; each q is the Benjamini-Hochberg false-discovery rate for that test over the 1,978 note-derived phenotypes tested, of which these rows are the curated subset of phenotypes that structured diagnosis codes rarely carry. Rows are grouped by organ system or domain. Where the curation vocabulary holds several names for one concept, a patient is counted once if any of them is present: severe obesity (morbid obesity, class III obesity); weight gain, documented (weight gain, abnormal weight gain); sleep-disordered breathing (snoring, sleep-disordered breathing, obstructive sleep apnea, sleep apnea, apnea-hypopnea, mixed sleep apnea, central sleep apnea); fatty liver disease (fatty liver disease, steatosis, hepatic steatosis, diffuse hepatic steatosis, nonalcoholic fatty liver disease, nonalcoholic steatohepatitis); perimenopause or menopause (perimenopause, perimenopausal symptoms, menopause, menopausal syndrome, menopausal symptoms, postmenopausal syndrome); bipolar disorder or schizophrenia (bipolar disorder, bipolar I disorder, bipolar II disorder, schizophrenia, schizoaffective disorder); substance use disorder (opioid use disorder, alcohol use disorder, substance abuse, cannabis use disorder, stimulant use disorder). Cells with counts <11 are reported as <11 per the privacy convention adopted in this study (Table 1).
Table 2.
Phenotypes extracted from clinical notes before treatment, by responder group. The four groups are the GLP-1 RA naive oral Wegovy initiators of Table 1 (N=3,011), classified by the best percent weight change within 180 days of the first prescription. A phenotype is present when the note-curation model recorded at least one affirmative mention of it (probability at or above 0.8) in a note dated on or before the index date, anywhere in the patient's available record with no look-back limit, the same pre-index window used for the comorbidities in Table 1. Cells are count (column percentage). The first P is from the chi-square test across the four groups and the second from Fisher's exact test comparing non-responders with super-responders alone; each q is the Benjamini-Hochberg false-discovery rate for that test over the 1,978 note-derived phenotypes tested, of which these rows are the curated subset of phenotypes that structured diagnosis codes rarely carry. Rows are grouped by organ system or domain. Where the curation vocabulary holds several names for one concept, a patient is counted once if any of them is present: severe obesity (morbid obesity, class III obesity); weight gain, documented (weight gain, abnormal weight gain); sleep-disordered breathing (snoring, sleep-disordered breathing, obstructive sleep apnea, sleep apnea, apnea-hypopnea, mixed sleep apnea, central sleep apnea); fatty liver disease (fatty liver disease, steatosis, hepatic steatosis, diffuse hepatic steatosis, nonalcoholic fatty liver disease, nonalcoholic steatohepatitis); perimenopause or menopause (perimenopause, perimenopausal symptoms, menopause, menopausal syndrome, menopausal symptoms, postmenopausal syndrome); bipolar disorder or schizophrenia (bipolar disorder, bipolar I disorder, bipolar II disorder, schizophrenia, schizoaffective disorder); substance use disorder (opioid use disorder, alcohol use disorder, substance abuse, cannabis use disorder, stimulant use disorder). Cells with counts <11 are reported as <11 per the privacy convention adopted in this study (Table 1).
| Phenotype | Non-responders (no loss) (N=750) | Responders (0 to 5% loss) (N=1,547) | Strong responders (5 to 10% loss) (N=549) | Super-responders (>10% loss) (N=165) | P (chi-square, 4 groups) | q (BH) | P (non- vs super-responders) | q (BH) |
|---|---|---|---|---|---|---|---|---|
| Weight history | ||||||||
| Severe obesity | 271 (36.1%) | 488 (31.5%) | 139 (25.3%) | 32 (19.4%) | <0.001 | 0.003 | <0.001 | 0.031 |
| Weight gain, documented | 450 (60.0%) | 1,038 (67.1%) | 378 (68.9%) | 106 (64.2%) | 0.002 | 0.262 | 0.333 | 1.000 |
| Eating behavior and appetite | ||||||||
| Hunger | 282 (37.6%) | 626 (40.5%) | 237 (43.2%) | 71 (43.0%) | 0.198 | 0.821 | 0.216 | 1.000 |
| Emotional eating | 56 (7.5%) | 124 (8.0%) | 58 (10.6%) | <11 (4.2%) | 0.043 | 0.720 | 0.174 | 1.000 |
| Disordered eating | 23 (3.1%) | 46 (3.0%) | 16 (2.9%) | 13 (7.9%) | 0.008 | 0.354 | 0.007 | 0.850 |
| Binge eating | 17 (2.3%) | 25 (1.6%) | <11 (1.6%) | <11 (0.6%) | 0.450 | 0.906 | 0.223 | 1.000 |
| Sleep and energy | ||||||||
| Snoring | 277 (36.9%) | 491 (31.7%) | 178 (32.4%) | 45 (27.3%) | 0.031 | 0.642 | 0.019 | 0.923 |
| Sleep-disordered breathing | 361 (48.1%) | 685 (44.3%) | 223 (40.6%) | 58 (35.2%) | 0.005 | 0.323 | 0.003 | 0.639 |
| Somnolence | 162 (21.6%) | 301 (19.5%) | 137 (25.0%) | 24 (14.5%) | 0.009 | 0.354 | 0.043 | 1.000 |
| Chronic fatigue | 77 (10.3%) | 121 (7.8%) | 51 (9.3%) | <11 (4.8%) | 0.067 | 0.731 | 0.037 | 1.000 |
| Metabolic and hepatic | ||||||||
| Impaired fasting glucose | 56 (7.5%) | 59 (3.8%) | 23 (4.2%) | <11 (3.0%) | <0.001 | 0.262 | 0.038 | 1.000 |
| Insulin resistance | 45 (6.0%) | 92 (5.9%) | 36 (6.6%) | <11 (4.8%) | 0.874 | 0.991 | 0.713 | 1.000 |
| Fatty liver disease | 137 (18.3%) | 250 (16.2%) | 77 (14.0%) | 20 (12.1%) | 0.098 | 0.742 | 0.068 | 1.000 |
| Gastrointestinal | ||||||||
| Nausea and vomiting | 324 (43.2%) | 598 (38.7%) | 195 (35.5%) | 63 (38.2%) | 0.038 | 0.694 | 0.258 | 1.000 |
| Gastroparesis | 17 (2.3%) | 20 (1.3%) | <11 (1.5%) | 0 (0.0%) | 0.113 | 0.775 | 0.054 | 1.000 |
| Reproductive and sexual health | ||||||||
| Perimenopause or menopause | 132 (17.6%) | 364 (23.5%) | 151 (27.5%) | 31 (18.8%) | <0.001 | 0.091 | 0.736 | 1.000 |
| Erectile dysfunction | 78 (10.4%) | 141 (9.1%) | 54 (9.8%) | <11 (4.2%) | 0.097 | 0.738 | 0.011 | 0.902 |
| Psychiatric and substance use | ||||||||
| Psychological trauma | 88 (11.7%) | 126 (8.1%) | 43 (7.8%) | 21 (12.7%) | 0.009 | 0.359 | 0.692 | 1.000 |
| Bipolar disorder or schizophrenia | 70 (9.3%) | 117 (7.6%) | 35 (6.4%) | <11 (3.6%) | 0.044 | 0.720 | 0.018 | 0.923 |
| Substance use disorder | 137 (18.3%) | 247 (16.0%) | 83 (15.1%) | 23 (13.9%) | 0.322 | 0.872 | 0.213 | 1.000 |
| Musculoskeletal | ||||||||
| Chronic low back pain | 108 (14.4%) | 224 (14.5%) | 77 (14.0%) | 13 (7.9%) | 0.137 | 0.804 | 0.030 | 1.000 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.