

Submitted:
17 October 2026
Posted:
20 October 2026
You are already at the latest version
Abstract
This paper examines the inferential framework used to attribute the positive association between acid-suppressive therapy (AS) and esophageal adenocarcinoma (EAC) to confounding by gastroesophageal reflux disease (GERD), a common indication for AS. The experimental literature has proposed several mechanisms by which AS may increase the risk of EAC—either by altering the properties of refluxate or enhancing proliferation in reflux-injured tissue—and reviews of the in vivo literature have suggested that the AS–EAC association may be causal. At the same time, clinical guidelines have long maintained that the AS–EAC association reflects confounding by GERD, and cite observational studies that estimate either the AS–EAC association among those without GERD or the treatment odds ratio upon adjusting for GERD as a main-effect covariate. This paper first outlines the causal hypotheses articulated in the in vivo literature and establishes that the patient's underlying reflux burden is an effect modifier under each of these hypotheses. It then argues that the epidemiologic findings presented in clinical guidelines as reassuring evidence against causality have been widely misread, as they do not inherently distinguish confounding by GERD from the causal structures implied by any of these hypotheses.
Keywords:
acid suppression
; gastroesophageal reflux disease
; GERD
; Barrett’s esophagus
; esophageal adenocarcinoma
; proton pump inhibitors
; H2-receptor antagonists
; confounding by indication
; effect modification
; causal inference
1. Introduction
The annual incidence of esophageal adenocarcinoma (EAC) increased in the United States by more than 750% between 1973 and 2017, the highest growth rate of any epithelial malignancy during that period; melanoma ranked second at approximately 275% [1]. EAC is thought to arise from chronic exposure of the distal esophagus to refluxed gastric and duodenal contents (e.g. acid, bile), and gastroesophageal reflux disease (GERD) is an established risk factor in EAC etiology [2]. Approximately 10% of those with reflux symptoms who undergo upper endoscopy are found to have Barrett’s esophagus (BE), the precursor lesion to EAC [3], and 0.1-0.5% of those with BE will progress to EAC in any given year, with a higher progression rate among those with dysplasia [4]. Though trends in obesity are thought to partially explain the increased prevalence of GERD [5], it is generally unclear why certain GERD patients develop BE/EAC while others do not [3].
Symptoms of GERD are commonly treated with acid-suppressive therapy (AS), traditionally through the use of proton pump inhibitors (PPIs) and H2-receptor antagonists (H2RAs) [6]. Despite evidence that acid can damage DNA [7], the experimental literature has proposed several hypotheses by which the use of AS may nevertheless increase the risk of EAC. These hypotheses suggest that by increasing gastric pH, AS modulates the composition [8,9,10] and solubility [8,11,12,13] of specific reflux constituents implicated in EAC pathogenesis [9,11,12,14], and separately promotes the progression to EAC by enhancing proliferation in reflux-conditioned tissue [15,16,17,18]. There is moreover a cluster of in vivo studies reporting higher rates of EAC, dysplasia, or BE under less acidic conditions [9,11,15,19,20,21], and although the results of these studies are heterogeneous [22,23], reviews of the animal literature have suggested that the use of AS may explain the rise in EAC incidence [10,12].
Observational studies often report a positive association between EAC and the use of AS [24,25,26,27,28], but clinical guidelines have long maintained that this association reflects confounding by GERD, whereby acidic reflux promotes BE/EAC and the use of AS is a benign marker of risk [29,30]. This interpretation [29,30] appears to be largely informed by the findings of a small collection of studies that estimate either the AS–EAC association among those without reflux-related indications [26] or the common treatment odds ratio (OR) after adjusting for predictors of reflux burden (e.g. GERD diagnosis, hiatal hernia, BMI) as main-effect covariates [25,26,31]. Though these estimates are elevated in general, their statistical nonsignificance appears to have been widely read as reassuring evidence that the AS–EAC association is non-causal [29,30,32], including in current clinical guidelines on the management of GERD [30].
This paper does not argue that AS contributes to EAC risk in human populations but rather that the findings of these observational studies have been interpreted within an inferential framework that is misaligned with the experimental literature. The statistical non-significance of the estimates reported in these studies may be read [29,30,32] as evidence against a GERD-independent causal effect under a loose evidentiary standard. However, the hypotheses of the experimental literature do not posit the existence of such an effect: they presuppose that the patient’s underlying reflux burden determines the duration of esophageal exposure to refluxate that is modified by AS, or that it determines the cellular context (e.g. mutational burden, receptor expression) in which the hormonal effects of AS are exerted. In this setting, the findings of these observational studies do not inherently distinguish confounding by GERD from a causal signal, and they cannot be read as reassuring evidence against causality.
2. Reflux Burden as an Effect Modifier
In a 2015 review of rat reflux models, Greene et al. [12] conclude that the suppression of gastric acidity in rats appears to “potentiate the development of esophageal adenocarcinoma" [12] and point to two mechanisms articulated in the reviewed studies. The first concerns the pH-dependent toxicity of bile [9,11], a reflux constituent that is suspected to be a central driver in BE/EAC pathogenesis [33,34]: while many bile acids precipitate irreversibly in normal gastric acidity [35,36], weakly acidic conditions maintain many bile species in a soluble state from which they can passively diffuse through cell membranes [13,37,38]. The second mechanism concerns the bacterial reduction of nitrate to nitrite, which Fein et al. [9] had speculated to facilitate the formation of carcinogenic N-nitroso compounds.
These hypothesized mechanisms are illustrated in Figure 1. Under these mechanisms, the use of AS alters the carcinogenicity of refluxate, but (treated) reflux burden determines the magnitude of esophageal exposure to that refluxate. As such, no causal effect exists in the absence of reflux, and the magnitude of this effect on risk generally increases with (treated) reflux burden. Several other proposed mechanisms can be represented similarly [8,10,39].
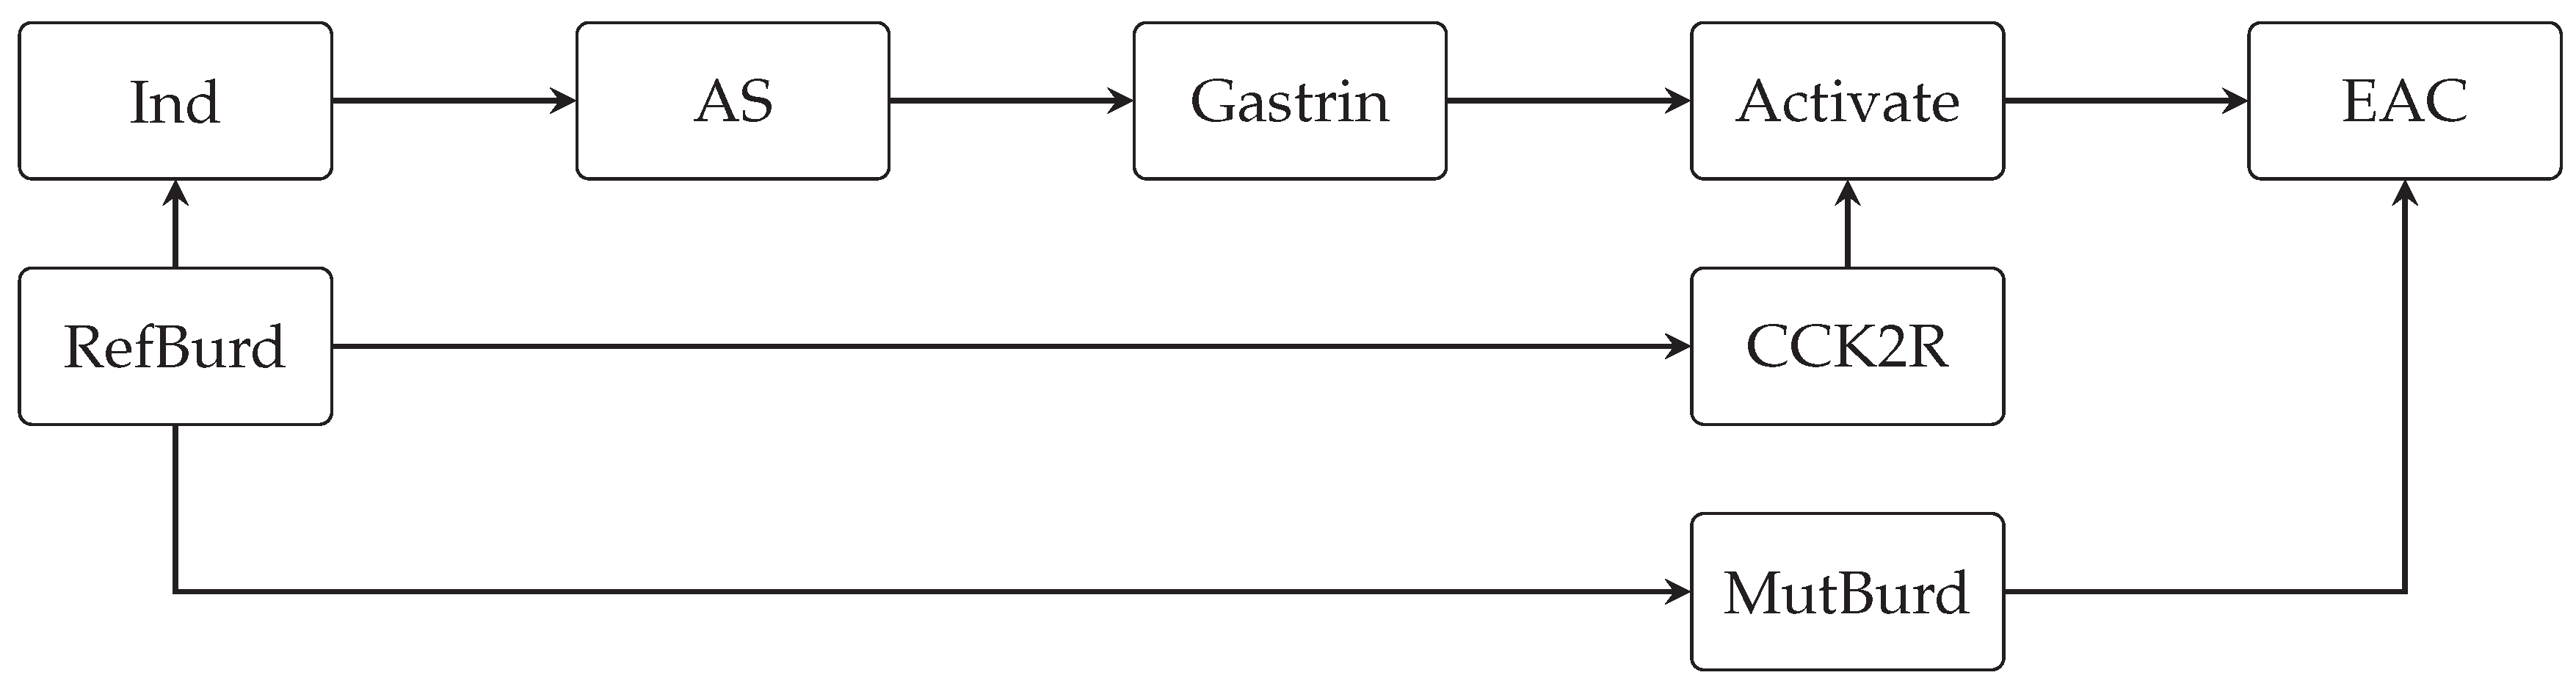
Next, consider the subsequent mouse model of Lee et al. [15], in which the authors examine the hypothesis that PPI-induced hypergastrinemia could promote the progression from BE to EAC [17,18]. The use of AS promotes secondary hypergastrinemia [40], and gastrin can function as a pro-oncogenic stimulus [16,17,41]. Separately, reflux-related inflammation damages DNA [42] and appears to enhance tissue responsiveness to gastrin through upregulation of the receptor CCK2R [15,18]. Consistent with an interactive effect, Lee et al. observe that PPI-induced hypergastrinemia promotes the development and dysplastic progression of Barrett’s-like metaplasia in chronically inflamed mouse esophagi, but do not observe any metaplastic alteration in mouse esophagi that lack the inflammatory stimulus [15].
This hypothesized mechanism is illustrated in Figure 2. Under this mechanism, the use of AS promotes hypergastrinemia, but the carcinogenic susceptibility to this pro-oncogenic stimulus depends on the prior accumulation of reflux-related cellular changes, namely CCK2R overexpression and mutational burden. Accordingly, the effect on EAC risk generally increases with (historical) reflux burden, and unless there is a widespread alternative source of esophageal injury that mimics the cellular context produced by chronic reflux—a source that does not appear to exist [12,43]—then virtually no effect on risk manifests in patients who do not experience reflux.
3. Epidemiologic Findings and Their Interpretations
The causal hypotheses proposed in the experimental literature presuppose that the effect of AS on EAC risk would depend on reflux burden, yet the source of the AS–EAC association seems to have been adjudicated within a framework that omits this possibility. In what appears to be regarded as the most probative observational study on the source of the AS–EAC association [29,30,32], Garcia Rodriguez et al. [26] make this framework explicit: “Long term pharmacological gastric acid suppression is a marker of increased risk... However these associations are most likely explained by the underlying treatment indications being a risk factor for the cancer rather than an independent harmful effect of these agents per se." Within this binary, GERD-independent causation is the only form of causation, and it would therefore suffice to observe evidence for the absence of a GERD-independent causal effect in order to infer the absence of causality in general. In practice, this implies that a near-null AS–EAC association among those without GERD would be sufficient to determine that an elevated association among those with GERD is non-causal.
Garcia Rodriguez et al. [26] distinguish long-term (3+ years) AS users with esophageal indications (e.g. reflux symptoms, esophagitis, BE) from long-term users with non-esophageal indications (e.g. peptic ulcer disease, gastritis) and estimate separate ORs for each group computed against a common referent of non-users. The authors observe that the OR is statistically significant for the esophageal group (OR: 5.42; 95% CI: [3.13, 9.39]) and statistically non-significant for the non-esophageal group (OR: 1.74; 95% CI: [0.90, 3.34]), and Spechler et al. [29] present this finding in a technical review for the American Gastroenterological Association (AGA):
PPI therapy also has effects that, conceivably, might promote the development of cancer in Barrett’s esophagus. For example, use of PPIs often is associated with an increase in the serum levels of gastrin, a hormone that has been shown to increase proliferation in Barrett’s epithelium... Garcia Rodriguez et al. found that patients who were treated with acid suppression for an ‘esophageal indication’ such as GERD had a significantly increased risk of developing esophageal adenocarcinoma… In contrast, for patients who were treated with acid suppression for a ‘gastroduodenal indication’ such as peptic ulcer disease, there was no significantly increased risk of adenocarcinoma... The lack of an association with cancer in patients taking PPIs for gastroduodenal disease suggests that the positive association in the patients with esophageal disease resulted from confounding by indication. In other words, it was likely the GERD, not the GERD treatment, that increased the incidence of cancer.
Spechler et al. appear to recognize what they consider to be evidence against an independent causal effect and subsequently infer the presence of confounding by GERD. However, this inference does not follow from the premise that the authors themselves articulate: if AS-induced hypergastrinemia promotes the progression from BE to EAC by increasing proliferation in BE [18,41]—a tissue context characterized by heightened responsiveness to gastrin [15,41] and a substantial mutational burden [44]—then one would only expect to observe an effect among those with BE or perhaps the GERD that causes it [3]—both are esophageal indications [26].
More generally, the stratification performed by Garcia Rodriguez et al. creates a contrast between those who would tend to have a pathological reflux burden and those who would not. Because the non-esophageal group’s OR (1.74; 95% CI: [0.90, 3.34]) is perfectly compatible with hypotheses that predict a relatively small effect on risk in those with small reflux burdens (or no effect in those without large reflux burdens), it would not by itself weigh against the causal hypotheses of the in vivo literature. Moreover, the group ORs are structured so that any of the causal hypotheses would predict a greater OR for the esophageal group than for the non-esophageal group. Let be the EAC odds for the common untreated reference group, let and be the baseline risks for the esophageal and non-esophageal groups, respectively, and let and be the change in absolute risk attributable to treatment. The OR for group i is given by:
As GERD is an established risk factor for EAC [2], we can assume that , and because the typical reflux burden is larger in the esophageal group than in the non-esophageal group, each of the mechanisms through which AS has been hypothesized to contribute to EAC risk would increase risk such that . It then follows straightforwardly that each of these hypothesized mechanisms would be expected to produce a causal signal where , and we cannot therefore infer from the non-esophageal group’s OR that the esophageal group’s OR reflects confounding by GERD as opposed to a causal effect.
A similar interpretive constraint applies in the context of main-effect regression adjustment [24,25,26,28,45]. As an illustrative example, consider Chow et al. [25], in which the authors report that the OR for 4 or more H2RA prescriptions attenuates from 4 (95% CI: [1.3, 12.4]) to 1.5 (95% CI: [0.4, 5.4]) after adjusting for the presence of reflux-related conditions as main-effect covariates, while also reporting “no excess risk” among those without said conditions. Both the authors and the AGA technical review quoted above interpret these findings as affirmative evidence against causality, but this could only be the case if a causal signal were expected in those without reflux-related conditions and the unreported treatment OR among those without said conditions were incompatible with even a small effect on risk.
Alternatively, the common GERD-adjusted treatment OR would not itself weigh against a causal effect as—in addition to being elevated—it may still understate the treatment OR among those with reflux-related conditions, i.e. those for whom AS would be predicted to have the greatest effect on risk. If we take the authors’ words to imply that the treatment OR among those without reflux-related conditions is smaller than 1.5, it would at least be suggestive of a larger treatment OR within some subset of individuals with reflux-related conditions, and the authors do not present any affirmative evidence suggesting that this elevated treatment OR would be non-causal. This argument also applies to the GERD-adjusted treatment ORs presented by Garcia Rodriguez et al. [26], as well as to the estimates presented in subsequent studies [45,46,47].
4. Discussion
In a context where positive but statistically non-significant associations are read as null associations [25,29,30], a causal signal may only be distinguishable among those with pathological reflux. That said, the interpretability of a treatment OR in some high-reflux stratum is still limited by the available proxy for reflux burden. A GERD diagnosis can itself correspond to a wide range of underlying reflux burdens [48] such that a positive treatment OR within the GERD-positive stratum may still reflect confounding by GERD. Self-reported symptom severity can instead be stratified finely [31], but it is inherently influenced by treatment [49] such that the group with the greatest underlying reflux burden may not be identifiable.
A distinct but closely related subliterature examines whether PPIs may be chemopreventive among those who have already progressed to BE, consisting primarily of observational studies that compare PPI users with non-users (including H2RA users) and a randomized controlled trial (AspECT) [50] that compares high and low doses of esomeprazole [51,52]. Whether epidemiologic evidence concerning PPI chemoprevention among those with BE can adjudicate the source of the AS–EAC association observed in the general population requires distinguishing three questions: first, whether the evidence genuinely supports a chemopreventive effect of PPIs among those with BE; second, whether any such protectiveness would generalize to those who have not yet developed BE; and third, whether such evidence bears on the safety or protectiveness of H2RAs.
Regarding the first question, a recent meta-analysis reported an adjusted OR of 0.46 (95% CI: [0.25, 0.86]) for PPI use among those with BE, but it also reported significant heterogeneity () and determined that the results of each observational study were at risk of either serious or critical bias (ROBINS-I) [51]. While the AspECT trial observed a trend towards superior EAC-related outcomes within the high-dose group [50], this would only necessarily constitute evidence of chemoprevention (and safety) if the safety of the lower dose is established elsewhere or if the PPI dose-risk curve is monotonic. This monotonicity is not guaranteed because the toxicity of bile acids is non-monotonic across the acidic pH spectrum [37,38] and PPIs possess pleiotropic effects [22,53,54,55]. PPI pleiotropy has been discussed within the in vivo literature [12,22] and could plausibly explain why the AspECT trial’s primary endpoint was substantially driven by non-EAC mortality, which was lower in the high-dose group [50].
As for the second question, if PPIs were to exert a protective effect in BE via increased gastric pH [29] or reduced refluxate volume [11], then there would not be an obvious reason as to why this protectiveness would be stage specific. If this protectiveness instead reflected a pleiotropic effect that manifests at a later stage of carcinogenesis [54,55], then protectiveness among those with BE would still be compatible with PPIs contributing to both BE pathogenesis and marginal EAC risk. To the third and final question, the protectiveness of PPIs would not speak to the safety of H2RAs insofar as this protective effect could reflect PPI-specific pleiotropy [22,53,54], a reduction in refluxate volume that is not achieved by H2RAs [56], or a more complete and prolonged suppression of gastric acidity [57] that maintains certain bile species in an ionized state [8,37] for a greater duration than do H2RAs.
To conclude, this paper does not argue that AS contributes to EAC risk in human populations but that the presumption to the contrary may be unwarranted. The in vivo literature establishes the biological plausibility of a causal role for AS in EAC etiology [11,12,15,19], and the epidemiologic findings that had been thought to best adjudicate the causal question do not do so [25,26]. Until the risk associated with untreated reflux has been adequately separated from the treatment that it precipitates, the AS–EAC association should not be dismissed as spurious.
Funding
The author received no funding for this work.
Conflicts of Interest
The author declares no competing interests.
References
- Hang, T.V.P.; Spiritos, Z.; Gamboa, A.M.; Chen, Z.; Force, S.; Patel, V.; Chawla, S.; Keilin, S.; Saba, N.F.; El-Rayes, B.; et al. Epidemiology of Early Esophageal Adenocarcinoma. Clin. Endosc. 2022, 55, 372–380. [Google Scholar] [CrossRef] [PubMed]
- Iijima, K. Etiologic factors for Barrett’s esophagus: toward countermeasures in Asia. Expert Rev. Gastroenterol. Hepatol. 2024, 18, 407–420. [Google Scholar] [CrossRef] [PubMed]
- Souza, R.F.; Spechler, S.J. Mechanisms and pathophysiology of Barrett oesophagus. Nat. Rev. Gastroenterol. Hepatol. 2022, 19, 605–620. [Google Scholar] [CrossRef] [PubMed]
- Kota, L.; Tyberg, A. Risk of Barrett’s esophagus progression to esophageal adenocarcinoma. Clin. Endosc. 2024, 57, 763–764. [Google Scholar] [CrossRef] [PubMed]
- Mao, Y.; Zhang, Y.; Hu, L.; Zhang, W.; An, Y.; Zhao, Y.; Tang, X. Association between body mass index at different levels and risk of gastroesophageal reflux disease: a systematic review with dose-response meta-analysis. Front. Physiol. 2025, 16, 1675457. [Google Scholar] [CrossRef] [PubMed]
- Al-Frejat, Z.; Martini, N.; Esper, A.; Al-Frejat, D.; Younes, S.; Hanna, M. GERD: Latest update on acid-suppressant drugs. Curr. Res. Pharmacol. Drug Discov. 2024, 7, 100198. [Google Scholar] [CrossRef] [PubMed]
- Jolly, A.J.; Wild, C.P.; Hardie, L.J. Acid and bile salts induce DNA damage in human oesophageal cell lines. Mutagenesis 2004, 19, 319–324. [Google Scholar] [CrossRef] [PubMed]
- Theisen, J.; Nehra, D.; Citron, D.; Johansson, J.; Hagen, J.A.; Crookes, P.E.; DeMeester, S.R.; Bremner, C.G.; DeMeester, T.R.; Peters, J.H. Suppression of gastric acid secretion in patients with gastroesophageal reflux disease results in gastric bacterial overgrowth and deconjugation of bile acids. J. Gastrointest. Surg. 2000, 4, 50–54. [Google Scholar] [CrossRef] [PubMed]
- Fein, M.; Peters, J.H.; Chandrasoma, P.; Ireland, A.P.; Oberg, S.; Ritter, M.P.; Bremner, C.G.; Hagen, J.A.; DeMeester, T.R. Duodenoesophageal reflux induces esophageal adenocarcinoma without exogenous carcinogen. J. Gastrointest. Surg. 1998, 2, 260–268. [Google Scholar] [CrossRef] [PubMed]
- Mirvish, S.S. Studies on experimental animals involving surgical procedures and/or nitrosamine treatment related to the etiology of esophageal adenocarcinoma. Cancer Lett. 1997, 117, 161–174. [Google Scholar] [CrossRef] [PubMed]
- Nasr, A.O.; Dillon, M.F.; Conlon, S.; Downey, P.; Chen, G.; Ireland, A.; Leen, E.; Bouchier-Hayes, D.; Walsh, T.N. Acid suppression increases rates of Barrett’s esophagus and esophageal injury in the presence of duodenal reflux. Surgery 2012, 151, 382–390. [Google Scholar] [CrossRef] [PubMed]
- Greene, C.L.; Worrell, S.G.; DeMeester, T.R. Rat Reflux Model of Esophageal Cancer and Its Implication in Human Disease. Ann. Surg. 2015, 262, 910–924. [Google Scholar] [CrossRef] [PubMed]
- Kauer, W.K.H.; Stein, H.J. Emerging concepts of bile reflux in the constellation of gastroesophageal reflux disease. J. Gastrointest. Surg. 2010, 14, S9–S16. [Google Scholar] [CrossRef] [PubMed]
- Fujimura, T.; Oyama, K.; Sasaki, S.; Nishijima, K.; Miyashita, T.; Ohta, T.; Miwa, K.; Hattori, T. Inflammation-Related Carcinogenesis and Prevention in Esophageal Adenocarcinoma Using Rat Duodenoesophageal Reflux Models. Cancers 2011, 3, 3206–3224. [Google Scholar] [CrossRef] [PubMed]
- Lee, Y.; Urbanska, A.M.; Hayakawa, Y.; Wang, H.; Au, A.S.; Luna, A.M.; Chang, W.; Jin, G.; Bhagat, G.; Abrams, J.A.; et al. Gastrin stimulates a cholecystokinin-2-receptor-expressing cardia progenitor cell and promotes progression of Barrett’s-like esophagus. Oncotarget 2017, 8, 203–214. [Google Scholar] [CrossRef] [PubMed]
- Harris, J.C.; Clarke, P.A.; Awan, A.; Jankowski, J.; Watson, S.A. An antiapoptotic role for gastrin and the gastrin/CCK-2 receptor in Barrett’s esophagus. Cancer Res. 2004, 64, 1915–1919. [Google Scholar] [CrossRef] [PubMed]
- Haigh, C.R.; Attwood, S.E.A.; Thompson, D.G.; Jankowski, J.A.; Kirton, C.M.; Pritchard, D.M.; Varro, A.; Dimaline, R. Gastrin Induces Proliferation in Barrett’s Metaplasia Through Activation of the CCK2 Receptor. Gastroenterology 2003, 124, 615–625. [Google Scholar] [CrossRef] [PubMed]
- Quante, M.; Abrams, J.A.; Lee, Y.; Wang, T.C. Barrett esophagus: What a mouse model can teach us about human disease. Cell Cycle 2012, 11, 4328–4338. [Google Scholar] [CrossRef] [PubMed]
- Dall’Olmo, L.; Fassan, M.; Dassie, E.; Scarpa, M.; Realdon, S.; Cavallin, F.; Cagol, M.; Battaglia, G.; Pizzi, M.; Guzzardo, V.; et al. Role of Proton Pump Inhibitor on Esophageal Carcinogenesis and Pancreatic Acinar Cell Metaplasia Development: An Experimental In Vivo Study. PLoS ONE 2014, 9, e112862. [Google Scholar] [CrossRef] [PubMed]
- Ireland, A.P.; Peters, J.H.; Smyrk, T.C.; DeMeester, T.R.; Clark, G.W.B.; Mirvish, S.S.; Adrian, T.E. Gastric Juice Protects Against the Development of Esophageal Adenocarcinoma in the Rat. Ann. Surg. 1996, 224, 358–371. [Google Scholar] [CrossRef] [PubMed]
- Cheng, P.; Li, J.S.; Gong, J.; Zhang, L.F.; Chen, R.Z. Effects of refluxate pH values on duodenogastroesophageal reflux-induced esophageal adenocarcinoma. World J. Gastroenterol. 2011, 17, 3060–3065. [Google Scholar] [CrossRef] [PubMed]
- Miyashita, T.; Shah, F.A.; Marti, G.P.; Wang, J.; Bonde, P.; Gibson, M.K.; Ohta, T.; Montgomery, E.A.; Duncan, M.; Harmon, J.W. Rabeprazole impedes the development of reflux-induced esophageal cancer in a surgical rat model. Dig. Dis. Sci. 2011, 56, 1309–1314. [Google Scholar] [CrossRef] [PubMed]
- Majka, J.; Wierdak, M.; Szlachcic, A.; Magierowski, M.; Targosz, A.; Urbanczyk, K.; Krzysiek-Maczka, G.; Ptak-Belowska, A.; Bakalarz, D.; Magierowska, K.; et al. Interaction of epidermal growth factor with COX-2 products and peroxisome proliferator-activated receptor-γ system in experimental rat Barrett’s esophagus. Am. J. Physiol.-Gastrointest. Liver Physiol. 2020, 318, G375–G389. [Google Scholar] [CrossRef] [PubMed]
- Lagergren, J.; Bergström, R.; Lindgren, A.; Nyrén, O. Symptomatic gastroesophageal reflux as a risk factor for esophageal adenocarcinoma. N. Engl. J. Med. 1999, 340, 825–831. [Google Scholar] [CrossRef] [PubMed]
- Chow, W.H.; Finkle, W.D.; McLaughlin, J.K.; Frankl, H.; Ziel, H.K.; Fraumeni, Jr., J.F. The Relation of Gastroesophageal Reflux Disease and Its Treatment to Adenocarcinomas of the Esophagus and Gastric Cardia. JAMA 1995, 274, 474–477. [Google Scholar] [CrossRef]
- García Rodríguez, L.A.; Lagergren, J.; Lindblad, M. Gastric acid suppression and risk of oesophageal and gastric adenocarcinoma: a nested case control study in the UK. Gut 2006, 55, 1538–1544. [Google Scholar] [CrossRef] [PubMed]
- Brusselaers, N.; Engstrand, L.; Lagergren, J. Maintenance proton pump inhibition therapy and risk of oesophageal cancer. Cancer Epidemiol. 2018, 53, 172–177. [Google Scholar] [CrossRef] [PubMed]
- Choi, H.G.; Lee, H.K.; Kang, H.S.; Lim, H.; Kim, J.H.; Kim, J.H.; Kim, N.Y.; Cho, S.J.; Nam, E.S.; Min, K.W.; et al. Possible Association between the Use of Proton Pump Inhibitors and H2 Receptor Antagonists, and Esophageal Cancer: A Nested Case–Control Study Using a Korean National Health Screening Cohort. Pharmaceuticals 2022, 15, 517. [Google Scholar] [CrossRef] [PubMed]
- Spechler, S.J.; Sharma, P.; Souza, R.F.; Inadomi, J.M.; Shaheen, N.J.; Association, A.G. American Gastroenterological Association technical review on the management of Barrett’s esophagus. Gastroenterology 2011, 140, e18–e52. [Google Scholar] [CrossRef] [PubMed]
- Katz, P.O.; Dunbar, K.B.; Schnoll-Sussman, F.H.; Greer, K.B.; Yadlapati, R.; Spechler, S.J. ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease. Am. J. Gastroenterol. 2022, 117, 27–56. [Google Scholar] [CrossRef] [PubMed]
- Farrow, D.C.; Vaughan, T.L.; Sweeney, C.; Gammon, M.D.; Chow, W.H.; Risch, H.A.; Stanford, J.L.; Hansten, P.D.; Mayne, S.T.; Schoenberg, J.B.; et al. Gastroesophageal reflux disease, use of H2 receptor antagonists, and risk of esophageal and gastric cancer. Cancer Causes Control 2000, 11, 231–238. [Google Scholar] [CrossRef] [PubMed]
- Dunbar, K.B.; Spechler, S.J. The Effect of Proton Pump Inhibitors on Barrett’s Esophagus. Gastroenterol. Clin. N. Am. 2015, 44, 415–424. [Google Scholar] [CrossRef] [PubMed]
- Hu, Y.; Ye, X.; Wang, R.; Poon, K. Current research progress in the role of reactive oxygen species in esophageal adenocarcinoma. Transl. Cancer Res. 2021, 10, 1568–1577. [Google Scholar] [CrossRef] [PubMed]
- Iwaya, Y.; Goda, K.; Kako, S.; Hattori, H.; Miyazawa, T.; Hara, D.; Hashigami, K.; Hirayama, A.; Okamura, T.; Nagaya, T.; et al. Association between endoscopic evidence of bile reflux and Barrett’s esophagus: A large-scale case-control study. Dig. Liver Dis. 2024. [Google Scholar] [CrossRef] [PubMed]
- Barthlen, W.; Liebermann-Meffert, D.; Feussner, H.; Stein, H.J. Influence of pH on bile acid concentration in human, pig and commercial bile: Implications for ‘alkaline’ gastro-esophageal reflux. Dis. Esophagus 1994, 7, 127–130. [Google Scholar] [CrossRef]
- Armstrong, D.; Bennett, J.R.; Blum, A.L.; Dent, J.; De Dombal, F.T.; Galmiche, J.P.; Lundell, L.; Margulies, M.; Richter, J.E.; Spechler, S.J. Gastric mucosal toxicity of duodenal juice constituents in the rat. Dig. Dis. Sci. 1994. [Google Scholar] [CrossRef] [PubMed]
- Bus, P.; Siersema, P.D.; van Baal, J.W.P.M. Cell culture models for studying the development of Barrett’s esophagus: a systematic review. Cell. Oncol. 2012, 35, 149–161. [Google Scholar] [CrossRef] [PubMed]
- Nehra, D.; Howell, P.; Williams, C.P.; Pye, J.K.; Beynon, J. Toxic bile acids in gastro-oesophageal reflux disease: influence of gastric acidity. Gut 1999, 44, 598–602. [Google Scholar] [CrossRef] [PubMed]
- Feagins, L.A.; Zhang, H.Y.; Hormi-Carver, K.; Quinones, M.H.; Thomas, T.; Zhang, X.; Terada, L.S.; Spechler, S.J.; Souza, R.F. Acid has antiproliferative effects in nonneoplastic Barrett’s epithelial cells. Am. J. Gastroenterol. 2007, 102, 10–20. [Google Scholar] [CrossRef]
- Dacha, S.; Razvi, M.; Massaad, J.; Cai, Q.; Wehbi, M. Hypergastrinemia. Gastroenterol. Rep. 2015, 3, 201–208. [Google Scholar] [CrossRef] [PubMed]
- Abdalla, S.I.; Lao-Sirieix, P.; Novelli, M.R.; Lovat, L.B.; Sanderson, I.R.; Fitzgerald, R.C. Gastrin-induced cyclooxygenase-2 expression in Barrett’s carcinogenesis. Clin. Cancer Res. 2004, 10, 4784–4792. [Google Scholar] [CrossRef] [PubMed]
- Gokulan, R.C.; Garcia-Buitrago, M.T.; Zaika, A.I. From Genetics to Signaling Pathways: Molecular Pathogenesis of Esophageal Adenocarcinoma. Biochim. Et. Biophys. Acta (BBA) -Rev. Cancer 2019, 1872, 37–48. [Google Scholar] [CrossRef] [PubMed]
- Zamani, S.A.; Wu, L.; Black, E.L.; Bartram, A.; Ng, A.W.T.; Secrier, M.; Perelman, J.D.; Ustaoglu, A.; Ococks, E.; Jacobson, D.; et al. Integrated epidemiological and molecular data inform the relationship between precancer and cancer states of esophageal adenocarcinoma. Nat. Med. 2026, 32, 1805–1816. [Google Scholar] [CrossRef] [PubMed]
- Gregson, E.M.; Bornschein, J.; Fitzgerald, R.C. Genetic progression of Barrett’s oesophagus to oesophageal adenocarcinoma. Br. J. Cancer 2016, 115, 403–410. [Google Scholar] [CrossRef] [PubMed]
- Duan, L.; Wu, A.H.; Sullivan-Halley, J.; Bernstein, L. Antacid drug use and risk of esophageal and gastric adenocarcinomas in Los Angeles County. Cancer Epidemiol. Biomark. Prev. 2009, 18, 526–533. [Google Scholar] [CrossRef] [PubMed]
- Arai, J.; Niikura, R.; Hayakawa, Y.; Kawahara, T.; Honda, T.; Hasatani, K.; Yoshida, N.; Nishida, T.; Sumiyoshi, T.; Kiyotoki, S.; et al. Chemoprevention of Oesophageal Squamous-Cell Carcinoma and Adenocarcinoma: A Multicentre Retrospective Cohort Study. Digestion 2022, 103, 192–204. [Google Scholar] [CrossRef] [PubMed]
- Adami, H.O.; Andersen, I.T.; Heide-Jørgensen, U.; Chang, E.T.; Nørgaard, M.; Sørensen, H.T. Ranitidine Use and Risk of Upper Gastrointestinal Cancers. Cancer Epidemiol. Biomark. Prev. 2021, 30, 2302–2308. [Google Scholar] [CrossRef] [PubMed]
- Horton, A.J.; Clayton, S.B. Optimization of impedance-measured reflux events in GORD utilizing acid exposure time. BMC Gastroenterol. 2020, 20, 179. [Google Scholar] [CrossRef] [PubMed]
- Nason, K.S.; Wichienkuer, P.P.; Awais, O.; Schuchert, M.J.; Luketich, J.D.; O’Rourke, R.W.; Hunter, J.G.; Morris, C.D.; Jobe, B.A. Gastroesophageal Reflux Disease Symptom Severity, Proton Pump Inhibitor Use, and Esophageal Carcinogenesis. Arch. Surg. 2011, 146, 851–858. [Google Scholar] [CrossRef] [PubMed]
- Jankowski, J.A.Z.; de Caestecker, J.; Love, S.B.; Reilly, G.; Watson, P.; Sanders, S.; Ang, Y.; Morris, D.; Bhandari, P.; Brooks, C.; et al. Esomeprazole and aspirin in Barrett’s oesophagus (AspECT): a randomised factorial trial. Lancet 2018, 392, 400–408. [Google Scholar] [CrossRef] [PubMed]
- Ko, M.T.; Rizwanullah, A.; Jafri, Z.; Fung, A.; Alexandre, L. Chemoprevention of Barrett’s Esophagus: a Systematic Review and Comprehensive Assessment of Bias. Dis. Esophagus 2025, 38, doaf062. [Google Scholar] [CrossRef] [PubMed]
- Hu, Q.; Sun, T.T.; Hong, J.; Fang, J.Y.; Xiong, H.; Meltzer, S.J. Proton Pump Inhibitors Do Not Reduce the Risk of Esophageal Adenocarcinoma in Patients with Barrett’s Esophagus: A Systematic Review and Meta-Analysis. PLoS ONE 2017, 12, e0169691. [Google Scholar] [CrossRef] [PubMed]
- Huo, X.; et al. In oesophageal squamous cells exposed to acidic bile salt medium, omeprazole inhibits IL-8 expression through effects on NF-κB and AP-1 that are independent of acid inhibition. Gut 2014, 63, 1042–1050. [Google Scholar] [CrossRef] [PubMed]
- Miyashita, T.; Shah, F.A.; Harmon, J.W.; Marti, G.P.; Matsui, D.; Okamoto, K.; Makino, I.; Hayashi, H.; Oyama, K.; Nakagawara, H.; et al. Do proton pump inhibitors protect against cancer progression in GERD? Surg. Today 2013, 43, 831–837. [Google Scholar] [CrossRef] [PubMed]
- Chueca, E.; Apostolova, N.; Esplugues, J.V.; García-González, M.A.; Lanas, Á.; Piazuelo, E. Proton Pump Inhibitors Display Antitumor Effects in Barrett’s Adenocarcinoma Cells. Front. Pharmacol. 2016, 7, 452. [Google Scholar] [CrossRef] [PubMed]
- Navas, E.; Luis-Navarro, J.C. Utility of premedication with different regimens of omeprazole and ranitidine in the prevention of acid broncho-aspiration syndrome. Rev. Esp. De Anestesiol. Y Reanim. 1992, 39, 337–340. [Google Scholar]
- Abrahami, D.; McDonald, E.G.; Schnitzer, M.; Azoulay, L. Trends in acid suppressant drug prescriptions in primary care in the UK: a population-based cross-sectional study. BMJ Open 2020, 10, e041529. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Directed acyclic graph of refluxate-carcinogenicity hypotheses. Abbreviations: Ind, treatment indication; AS, acid suppression; RefCarc, refluxate carcinogenicity; EsoExp, esophageal exposure to refluxate; EAC, esophageal adenocarcinoma; RefBurd, reflux burden.
Figure 1.
Directed acyclic graph of refluxate-carcinogenicity hypotheses. Abbreviations: Ind, treatment indication; AS, acid suppression; RefCarc, refluxate carcinogenicity; EsoExp, esophageal exposure to refluxate; EAC, esophageal adenocarcinoma; RefBurd, reflux burden.
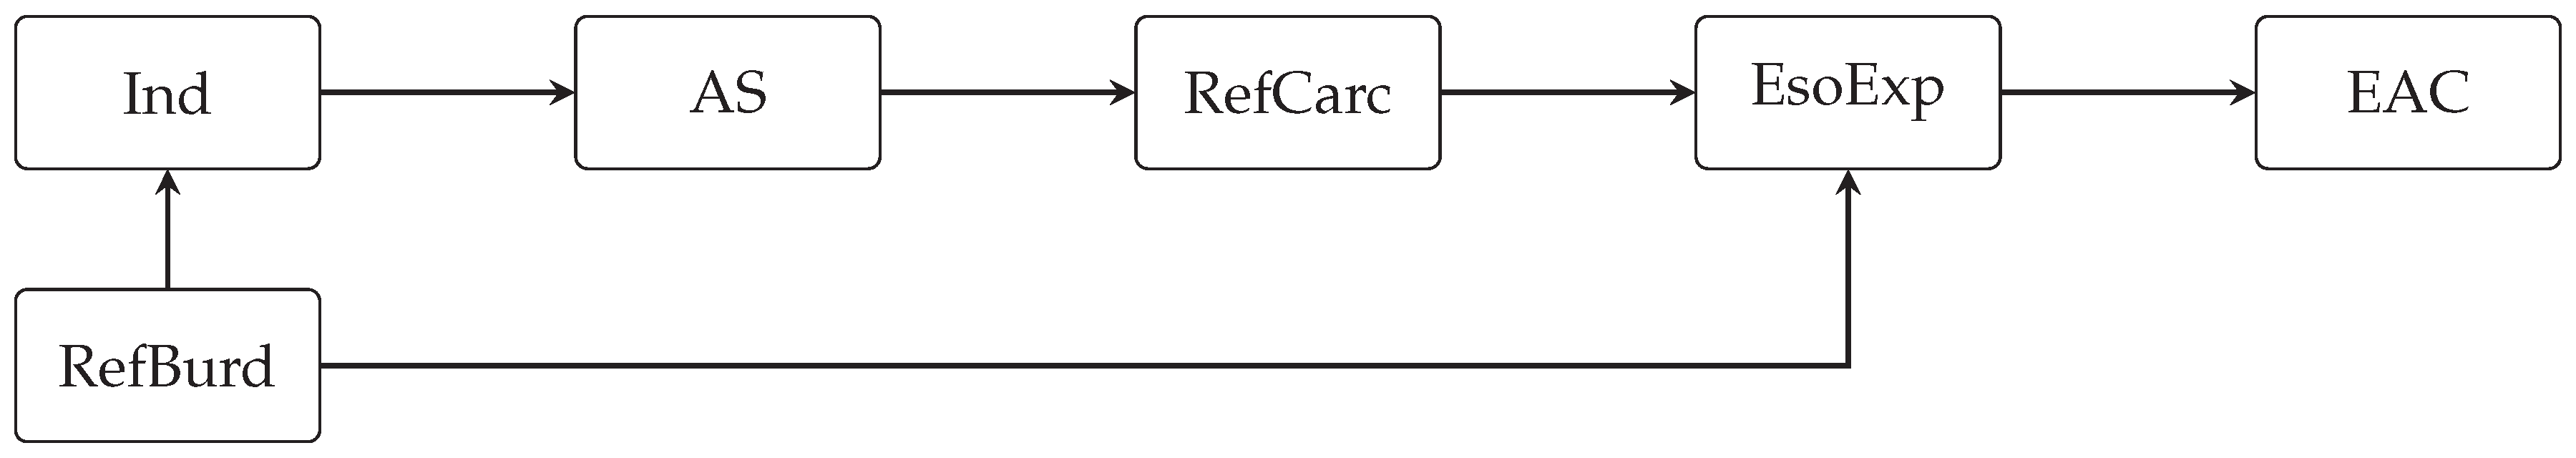
Figure 2.
Directed acyclic graph of hypergastrinemia hypothesis. Abbreviations: Ind, treatment indication; AS, acid suppression; Gastrin, serum gastrin concentration; Activate, CCK2R activation; EAC, esophageal adenocarcinoma; RefBurd, reflux burden; CCK2R, CCK2R expression; MutBurd, mutational burden.
Figure 2.
Directed acyclic graph of hypergastrinemia hypothesis. Abbreviations: Ind, treatment indication; AS, acid suppression; Gastrin, serum gastrin concentration; Activate, CCK2R activation; EAC, esophageal adenocarcinoma; RefBurd, reflux burden; CCK2R, CCK2R expression; MutBurd, mutational burden.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.