
Submitted:
14 September 2026
Posted:
16 September 2026
You are already at the latest version
Abstract
Background/Objectives: Menopausal hormone therapy (MHT) and alendronate improve bone mineral density (BMD), but their comparative effects on trabecular bone score (TBS) are unclear. We compared 12-month changes in TBS and site-specific BMD in postmenopausal women treated with MHT or alendronate. Methods: This retrospective cohort included 172 treatment-naïve postmenopausal women with newly diagnosed osteoporosis who initiated MHT (n=87) or alendronate 70 mg/week (n=85). Complete baseline and approximately 12-month DXA/TBS data were available for 164 women (MHT, n=83; alendronate, n=81). The primary outcome was the adjusted between-group difference in lumbar spine TBS at follow-up, assessed by analysis of covariance. Results: The adjusted MHT-minus-alendronate difference in TBS was 0.023 (95% CI, 0.010–0.036; P<0.001). TBS showed no significant within-group change with MHT (0.002 ± 0.044; P=0.699) but decreased with alendronate (−0.018 ± 0.040; P<0.001). BMD increased significantly in both groups, with greater gains with alendronate at the lumbar spine (adjusted difference, −0.014 g/cm2; 95% CI, −0.019 to −0.009; P<0.001), femoral neck (−0.005 g/cm2; 95% CI, −0.009 to −0.001; P=0.013), and total hip (−0.007 g/cm2; 95% CI, −0.011 to −0.003; P<0.001). Conclusions: Both treatments improved BMD, but alendronate produced larger gains, whereas no significant within-group change in TBS was observed with MHT. These findings suggest discordant treatment-related changes in BMD and TBS and warrant cautious interpretation because of the observational design and limitations of serial TBS monitoring.
Keywords:
alendronate
; bone mineral density
; menopausal hormone therapy
; postmenopausal women
; trabecular bone score
1. Introduction
The menopausal transition is accompanied by a marked decline in ovarian estrogen production, resulting in accelerated bone remodeling, an imbalance between bone resorption and formation, and progressive deterioration in skeletal strength. Although areal bone mineral density (BMD) measured by dual-energy X-ray absorptiometry (DXA) remains the cornerstone of osteoporosis diagnosis and treatment monitoring, BMD captures only one component of bone strength and does not fully account for individual differences in fracture susceptibility. Consequently, contemporary osteoporosis management increasingly emphasizes an integrated assessment incorporating bone mass, clinical risk factors, and complementary indices of skeletal quality [1,2].
Menopausal hormone therapy (MHT) and bisphosphonates are established antiresorptive approaches, but they are generally used in different clinical contexts. MHT prevents menopause-associated bone loss and reduces fracture risk, particularly in appropriately selected symptomatic women who are younger than 60 years or within 10 years of menopause onset [1,2,3]. In contrast, bisphosphonates are generally recommended as initial pharmacological therapy for postmenopausal women at high fracture risk. Alendronate has demonstrated sustained increases in BMD and significant reductions in vertebral and nonvertebral fractures in randomized clinical trials [1,4]. Thus, both therapies offer skeletal protection, but their distinct biological mechanisms and clinical indications may result in different patterns of response across measures of bone mass and bone quality.
Previous randomized studies comparing estrogen-based therapy with alendronate have shown that both interventions suppress bone turnover and increase BMD, while alendronate may produce larger gains at selected skeletal sites [5,6]. However, these trials were conducted largely before trabecular bone score became available in routine clinical practice and focused predominantly on changes in BMD. Similar gains in BMD may therefore coexist with different changes in DXA-derived trabecular texture as reflected by TBS.
Trabecular bone score (TBS) is a unitless index derived from gray-level variations in lumbar spine DXA images and provides information related to trabecular bone texture that is partly independent of BMD. Prospective cohort evidence has demonstrated that lower TBS is associated with increased fracture risk independently of conventional clinical risk factors and femoral neck BMD, and TBS may be used to refine FRAX-based fracture probability [7]. Recent ESCEO–IOF recommendations and the 2023 International Society for Clinical Densitometry Official Positions support its use as a complementary tool for fracture-risk assessment [8,9]. Nevertheless, its role in longitudinal treatment monitoring remains less firmly established. Treatment-related changes in TBS are generally smaller and more variable than corresponding BMD changes, particularly with antiresorptive therapies, and may differ according to the intervention, duration of treatment, and analytic algorithm used [8,9,10].
Contemporary head-to-head evidence comparing MHT and alendronate using both BMD and TBS as longitudinal outcomes remains limited. Evaluating these complementary measurements within the same cohort may clarify whether gains in bone mass are accompanied by parallel changes in trabecular bone texture or whether the two treatments generate distinct skeletal response profiles. Therefore, the present study compared the approximately 12-month changes in lumbar spine TBS and site-specific BMD among postmenopausal women receiving transdermal estradiol-based MHT, with continuous oral micronized progesterone added for women with an intact uterus, or weekly oral alendronate. The primary outcome was the adjusted between-group difference in lumbar spine TBS at approximately 12 months, accounting for baseline TBS, while lumbar spine, femoral neck, and total hip BMD were evaluated as secondary outcomes. Absolute changes from baseline were additionally examined to describe within- and between-group treatment responses.
2. Materials and Methods
2.1. Study Design and Setting
This retrospective, observational, comparative cohort study was conducted at the Banu Çiftçi Private Clinic, İstanbul, Türkiye, and included consecutive postmenopausal women who initiated study treatment between January 1, 2019, and April 1, 2025. The medical records of women who initiated either menopausal hormone therapy (MHT) or oral alendronate as part of routine clinical care were retrospectively reviewed. The study protocol was reviewed and approved by the Antalya Training and Research Hospital Ethics Committee on July 8, 2026 (Decision No. 12/3). The study was conducted in accordance with the principles of the Declaration of Helsinki and applicable national regulations.
The date on which the study treatment was initiated was considered the index date. Treatment allocation was not randomized and was determined before inclusion in the study according to the patient’s clinical characteristics, bone health status, treatment eligibility, preferences, and the clinical judgment of the treating physician. No treatment decision was made for research purposes.
The source cohort included 172 women, of whom 87 received MHT and 85 received alendronate. Complete baseline and approximately 12-month bone mineral density (BMD) and trabecular bone score (TBS) measurements were available for 164 participants, including 83 women in the MHT group and 81 women in the alendronate group. These participants constituted the primary complete-case analysis cohort. Participants without an evaluable follow-up examination remained in the study flow but were not included in the primary longitudinal outcome analyses.
2.2. Eligibility Criteria
Women were eligible if they had documented postmenopausal status, newly diagnosed postmenopausal osteoporosis, had not previously received pharmacological osteoporosis treatment, had newly initiated either the predefined MHT regimen or oral alendronate 70 mg once weekly, and had a baseline dual-energy X-ray absorptiometry examination that included both BMD and TBS assessment. Osteoporosis was defined by a T-score of ≤−2.5 at the lumbar spine, femoral neck, or total hip. Postmenopausal status was defined as at least 12 consecutive months of amenorrhea in the absence of another pathological or physiological cause. Women with documented secondary osteoporosis were excluded.
The baseline examination was defined as the DXA/TBS measurement performed within the 3 months preceding treatment initiation and considered representative of pretreatment bone status. When more than one examination was available within this period, the measurement closest to the index date was selected.
For the longitudinal analysis, participants were required to have a follow-up DXA/TBS examination performed approximately 12 months after treatment initiation. In the available cohort, follow-up examinations were performed between 11 and 14 months after the index date. When more than one examination was available within this period, the examination closest to 12 months was selected.
An additional requirement was that the baseline and follow-up examinations of each participant had been performed using the same DXA system. Participants were also excluded from the 12-month outcome analysis if the follow-up examination was unavailable, if treatment was discontinued before the follow-up assessment, if the participant switched to another bone-active therapy, or if follow-up could not be completed because of loss to follow-up, relocation, or death unrelated to bone treatment. Participants who received both study treatments concurrently or initiated another bone-active treatment before the 12-month assessment were likewise excluded from the corresponding comparative outcome analysis.
2.3. Treatment Protocols
Participants were classified according to the treatment initiated during routine clinical practice.
Participants in the MHT group received transdermal estradiol gel. Women with an intact uterus additionally received continuous oral micronized progesterone at a dose of 100 mg/day for endometrial protection, whereas women with a history of hysterectomy received estrogen alone. Transdermal estradiol was initiated at 0.5 mg/day and was subsequently individualized during routine clinical follow-up according to menopausal symptom control, clinical response, tolerability, and serum estradiol concentrations. Dose adjustments were performed according to the clinic’s routine treatment protocol, with the aim of maintaining serum estradiol concentrations within a target range of 60–150 pg/mL.
Participants in the comparator group received oral alendronate at a dose of 70 mg once weekly. Alendronate treatment was prescribed and monitored according to routine clinical practice.
Calcium and/or vitamin D supplementation was not standardized as part of the study intervention and was prescribed according to individual clinical requirements. Supplementation status was recorded separately and was considered in the adjusted statistical analyses.
Treatment adherence was evaluated from prescription records and follow-up documentation. Use of at least 80% of the prescribed treatment during the observation period was classified as adequate adherence. Treatment adherence was not used as a mandatory inclusion criterion for the primary analysis because it was a post-baseline characteristic; however, a sensitivity analysis restricted to participants with adherence of at least 80% was planned.
2.4. Data Collection and Clinical Variables
Demographic, clinical, treatment, and densitometric data were extracted retrospectively from electronic medical records, outpatient follow-up files, prescription records, and original DXA/TBS reports using a standardized data collection form.
The following baseline variables were recorded: age at treatment initiation, duration of menopause, body mass index, diabetes mellitus, history of fragility fracture, current smoking, and calcium and/or vitamin D supplementation. Treatment adherence was assessed separately during follow-up.
A previous fragility fracture was defined as a fracture occurring spontaneously or following low-energy trauma, such as a fall from standing height or lower. Current smoking was recorded as a binary variable based on the smoking status documented at treatment initiation.
Follow-up duration, follow-up completion status, month of attrition, reason for exclusion from the 12-month analysis, and whether baseline and follow-up measurements had been performed using the same DXA system were also recorded. Each participant was assigned a unique anonymized study identifier, and all directly identifiable personal information was removed before statistical analysis.
2.5. Bone Mineral Density Assessment
Bone mineral density was assessed by dual-energy X-ray absorptiometry using a GE Lunar iDXA system operated with enCORE software version 18, Service Pack 5. Areal BMD was recorded in g/cm2 at the lumbar spine (L1–L4), femoral neck, and total hip.
The absolute BMD values reported in the original DXA examinations were entered into the study database. No retrospective remeasurement or manual recalculation of BMD was performed for the purposes of the study.
For each participant, baseline and follow-up examinations were performed using the same DXA system. Participants whose serial measurements had been performed using different systems were not eligible for the longitudinal analysis.
2.6. Trabecular Bone Score Assessment
Trabecular bone score was derived from the texture of the anteroposterior lumbar spine DXA image at the L1–L4 region using TBS software version 3.10 (Medimaps) within the GE Lunar reporting environment. TBS analysis was based on the same lumbar spine DXA acquisition used for the BMD assessment and therefore did not require any additional imaging or radiation exposure.
The TBS value available in the original clinical bone health report was recorded for each examination. No new retrospective TBS analysis or reprocessing of archived DXA images was undertaken. Baseline and follow-up TBS values were obtained from examinations performed using the same DXA system for each individual participant.
2.7. Study Outcomes
The primary outcome was the adjusted between-group difference in lumbar spine TBS at approximately 12 months, with baseline TBS included as a covariate. Absolute change from baseline was additionally calculated for descriptive and unadjusted comparisons. Secondary outcomes were the corresponding adjusted between-group differences in lumbar spine, femoral neck, and total hip BMD at approximately 12 months.
2.8. Statistical Analysis
Statistical analyses were performed using IBM SPSS Statistics for Windows, version 25.0. Continuous variables were presented as mean ± standard deviation or median and interquartile range, and categorical variables as number and percentage. Normality was assessed using visual methods and the Shapiro–Wilk test.
Baseline characteristics were compared using the independent-samples t test or Mann–Whitney U test for continuous variables and the Pearson chi-square or Fisher’s exact test for categorical variables. Within-group changes were evaluated using the paired-samples t test or Wilcoxon signed-rank test. Absolute change scores were compared between groups using the independent-samples t test or Mann–Whitney U test, as appropriate.
Adjusted between-group comparisons were performed using analysis of covariance, with each 12-month TBS or BMD value as the dependent variable, treatment group as the main factor, and the corresponding baseline measurement as a covariate. Models were additionally adjusted for age, duration of menopause, baseline body mass index, diabetes mellitus, previous fragility fracture, current smoking, calcium and/or vitamin D supplementation, and follow-up duration. Adjusted mean differences were reported with 95% confidence intervals.
Analyses were based on complete cases, and missing outcomes were not imputed. A sensitivity analysis was conducted among participants with treatment adherence of at least 80%. All tests were two-sided, and P<0.05 was considered statistically significant.
3. Results
A total of 172 consecutive postmenopausal women met the eligibility criteria and were included in the baseline cohort; 87 initiated menopausal hormone therapy (MHT) and 85 initiated oral alendronate. The approximately 12-month evaluation was completed by 164 participants (95.3%), including 83 of 87 women in the MHT group (95.4%) and 81 of 85 women in the alendronate group (95.3%; P=1.000). Eight participants were not included in the longitudinal analysis: three were lost to follow-up, two discontinued treatment, one relocated, one died from a cause unrelated to bone treatment, and one switched to another bone-active treatment. The study flow is presented in Figure 1. All baseline and follow-up measurements for an individual participant were obtained using the same DXA system. Median follow-up duration was 12.3 months (interquartile range [IQR], 11.8–12.7) in the MHT group and 12.0 months (IQR, 11.7–12.4) in the alendronate group (P=0.037).
No statistically significant between-group differences were observed in the measured baseline demographic, clinical, or densitometric characteristics (Table 1). Mean age was 57.4 ± 2.7 years in the MHT group and 57.4 ± 3.0 years in the alendronate group, while mean duration of menopause was 6.8 ± 2.1 and 6.7 ± 2.1 years, respectively. Baseline lumbar spine, femoral neck, and total hip BMD values and baseline TBS were likewise similar between groups. Adequate treatment adherence was documented in 76 of 83 participants in the MHT group (91.6%) and 73 of 81 participants in the alendronate group (90.1%; P=0.749).
The primary adjusted analysis demonstrated a significant between-group difference in TBS at approximately 12 months (adjusted MHT-minus-alendronate difference, 0.023; 95% CI, 0.010 to 0.036; P<0.001) (Table 2). In descriptive within-group analyses, mean TBS showed no statistically significant change in the MHT group, increasing from 1.258 ± 0.058 at baseline to 1.260 ± 0.072 at follow-up (mean change, 0.002 ± 0.044; P=0.699). In contrast, mean TBS decreased from 1.257 ± 0.057 to 1.239 ± 0.070 in the alendronate group (mean change, −0.018 ± 0.040; P<0.001). The unadjusted between-group difference in change, calculated as MHT minus alendronate, was 0.020 (95% CI, 0.007 to 0.033; P=0.003).
Lumbar spine BMD increased significantly in both groups. The mean increase was 0.014 ± 0.018 g/cm2 in the MHT group and 0.028 ± 0.015 g/cm2 in the alendronate group (both P<0.001). The adjusted MHT-minus-alendronate difference was −0.014 g/cm2 (95% CI, −0.019 to −0.009; P<0.001), indicating a greater increase with alendronate. Femoral neck BMD increased by 0.006 ± 0.014 g/cm2 with MHT and by 0.012 ± 0.011 g/cm2 with alendronate (both P<0.001); the corresponding adjusted between-group difference was −0.005 g/cm2 (95% CI, −0.009 to −0.001; P=0.013). Total hip BMD increased by 0.008 ± 0.013 g/cm2 and 0.015 ± 0.012 g/cm2, respectively (both P<0.001), with an adjusted difference of −0.007 g/cm2 (95% CI, −0.011 to −0.003; P<0.001). Thus, alendronate was associated with larger BMD gains at all evaluated skeletal sites, whereas MHT was associated with a more favorable 12-month TBS response.
The sensitivity analysis restricted to the 149 participants with documented treatment adherence of at least 80% (MHT, n=76; alendronate, n=73) showed generally similar effect directions. The adjusted MHT-minus-alendronate difference remained significant for TBS (0.020; 95% CI, 0.006 to 0.034; P=0.005), lumbar spine BMD (−0.015 g/cm2; 95% CI, −0.020 to −0.009; P<0.001), and total hip BMD (−0.008 g/cm2; 95% CI, −0.012 to −0.003; P<0.001). The femoral neck difference was attenuated and was no longer statistically significant (−0.004 g/cm2; 95% CI, −0.008 to 0.000; P=0.070).
4. Discussion
In this retrospective comparative cohort study, both menopausal hormone therapy and weekly oral alendronate were associated with significant increases in BMD over approximately 12 months. Alendronate was associated with greater gains at the lumbar spine, femoral neck, and total hip in the primary adjusted analyses. In contrast, the two treatments showed different patterns of TBS change: TBS showed no statistically significant within-group change in the MHT group but decreased modestly in the alendronate group. The between-group difference in TBS remained significant after adjustment for baseline skeletal measurements and relevant clinical covariates. In the adherence-restricted sensitivity analysis, the overall pattern of effects was similar, although the between-group difference in femoral neck BMD was attenuated and no longer statistically significant. Collectively, these findings suggest that treatment-related changes in bone mass and DXA-derived trabecular texture may not necessarily progress in parallel. However, the results should not be interpreted as demonstrating the overall skeletal superiority of one treatment over the other.
The greater BMD gains observed with alendronate are consistent with previous head-to-head trials comparing alendronate with estrogen-based treatment. These studies demonstrated that both interventions suppressed bone turnover and increased BMD, although alendronate generally produced larger improvements at selected skeletal sites [5,6]. Alendronate strongly inhibits osteoclast-mediated bone resorption and permits progressive secondary mineralization of existing bone, which may contribute to the relatively pronounced increase in areal BMD. MHT acts primarily by correcting the estrogen-deficient state responsible for accelerated postmenopausal bone turnover and thereby prevents or reverses early postmenopausal bone loss. The significant increases observed in all three BMD regions in the MHT group therefore indicate a measurable skeletal response, even though their magnitude was smaller than that observed with alendronate. Because the two treatments are used in different clinical contexts, differences in BMD response should not be interpreted as direct evidence of differences in antifracture efficacy.
The absence of a statistically significant decline in TBS during MHT is biologically plausible and is consistent with previous evidence suggesting a favorable association between estrogen therapy and trabecular bone texture. In the population-based OsteoLaus cohort, current MHT users had higher TBS and BMD than past or never users, and the benefit appeared to persist for a period after treatment withdrawal [11]. In addition, HR-pQCT data from recently postmenopausal women showed that MHT preserved cortical vBMD and cortical structural parameters at the distal radius and attenuated loss of trabecular vBMD at the thoracic spine, although it did not prevent all trabecular microarchitectural changes at the radius [12]. Although those findings were obtained using different study designs and imaging techniques, they support the possibility that estrogen therapy may influence skeletal characteristics not completely captured by areal BMD. The present results add longitudinal information for a clinically individualized transdermal estradiol regimen, with continuous oral micronized progesterone used for endometrial protection in women with an intact uterus. Nevertheless, because TBS is an indirect texture index rather than a direct measurement of trabecular microarchitecture, the absence of a statistically significant decline in TBS should not be interpreted as proof of structural preservation or improvement.
The reduction in TBS observed in the alendronate group requires particularly cautious interpretation. The modest decrease in TBS observed in the alendronate group differs from previous reports in which bisphosphonate therapy was generally associated with small increases or relative stability in TBS despite substantially larger gains in BMD [10,13]. Furthermore, studies using high-resolution peripheral quantitative computed tomography have generally indicated that alendronate stabilizes or modestly improves aspects of density, microarchitecture, and estimated bone strength rather than causing structural deterioration [14]. Accordingly, the observed TBS reduction should not be interpreted as evidence that alendronate damages trabecular bone.
Several methodological considerations may explain the apparent discordance between BMD and TBS. TBS is derived from gray-level variations in lumbar DXA images and can be affected by acquisition conditions, positioning, soft-tissue distribution, image noise, and analytical precision. Although the statistically significant difference between groups reflects a group-level contrast, the absolute TBS changes were small. A statistically detectable mean difference does not necessarily indicate that changes in individual participants exceeded measurement variability. The 2019 ISCD position proposed a conservative least significant change of approximately 5.8% when a facility-specific precision estimate is unavailable [15]. More importantly, the 2023 ISCD Official Positions state that monitoring and reporting changes in TBS are unlikely to be clinically helpful with the current TBS algorithm [9]. Thus, the TBS findings in this study should be viewed as exploratory and hypothesis-generating rather than as evidence supporting the use of serial TBS measurements to determine treatment success or failure in an individual patient.
The contrast between greater BMD gains with alendronate and the different 12-month TBS response observed with MHT further emphasizes that BMD and TBS are related but noninterchangeable measures. BMD primarily quantifies mineral content projected over bone area, whereas TBS provides complementary information derived from lumbar spine image texture. A change in one measure is therefore not required to be proportional to a change in the other. From a clinical perspective, the present findings do not support choosing MHT instead of alendronate solely to obtain a more favorable TBS value, nor do they diminish the established role of alendronate in women at elevated fracture risk. Treatment selection should continue to be based on the patient’s age, time since menopause, menopausal symptoms, fracture risk, contraindications, preferences, and the overall benefit–risk profile [1,2]. BMD remains the principal densitometric measure for monitoring treatment, while TBS is more appropriately used as a complementary component of fracture-risk assessment [8,9].
The study has several strengths. It provides a direct real-world comparison of two frequently used but clinically distinct antiresorptive strategies and evaluates both conventional BMD and TBS within the same cohort. Baseline and follow-up measurements for each participant were obtained using the same DXA system, reducing within-participant variability related to device changes. The MHT regimen was well defined, retention at approximately 12 months was high, and the overall pattern of findings was robust to multivariable adjustment and broadly similar in the adherence-restricted sensitivity analysis, although the between-group difference in femoral neck BMD was attenuated in the latter. Evaluation of three skeletal BMD sites alongside TBS also allowed a broader assessment of the skeletal response than reliance on lumbar spine BMD alone.
Several limitations should nevertheless be acknowledged. First, the retrospective and nonrandomized design introduces the possibility of selection bias, confounding by indication, and residual confounding. Women selected for MHT and those selected for alendronate may have differed in clinical characteristics that were not captured in the database, even though the measured baseline variables were similar. Second, the observation period was limited to approximately 12 months, preventing assessment of longer-term skeletal changes. Third, the study was not designed or powered to compare fracture outcomes, and the observed differences in surrogate densitometric measurements cannot be translated directly into differences in fracture protection. Bone turnover markers, FRAX probabilities, detailed dietary and physical activity data, waist circumference, and other factors potentially affecting BMD or TBS were unavailable. In addition, facility-specific precision errors and least significant change values for TBS were not available, limiting interpretation of the clinical significance of individual TBS changes. The single-center setting and relatively modest sample size may also limit the generalizability of the findings. Finally, the complete-case approach may have introduced attrition bias, although follow-up completion was high and similar between the two groups.
In conclusion, both MHT and alendronate were associated with significant improvements in BMD over approximately 12 months, with larger gains observed with alendronate at the lumbar spine, femoral neck, and total hip. TBS showed no statistically significant within-group change during MHT, whereas a modest decrease was observed during alendronate treatment. This discordance suggests that BMD and TBS may capture different aspects of the skeletal response; however, the TBS findings should be interpreted cautiously because of the small absolute changes, the limitations of serial TBS monitoring, and the observational study design. Prospective studies incorporating standardized precision assessment, longer follow-up, bone turnover markers, and fracture outcomes are needed to determine whether treatment-specific differences in TBS have independent clinical significance.
Author Contributions
Conceptualization, B.Ç. and B.K.; methodology, B.Ç. and B.K.; investigation, B.Ç.; data curation, B.Ç.; formal analysis, B.K.; validation, B.Ç. and B.K.; writing—original draft preparation, B.Ç. and B.K.; writing—review and editing, B.Ç. and B.K.; supervision, B.K.; project administration, B.Ç. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Antalya Training and Research Hospital Ethics Committee (decision no. 12/3; 8 July 2026).
Informed Consent Statement
Written informed consent for the use of anonymized clinical data for scientific research was obtained from all participants.
Data Availability Statement
The data supporting the findings of this study are available from the corresponding author upon reasonable request. The data are not publicly available owing to privacy and ethical restrictions.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Eastell, R.; Rosen, C.J.; Black, D.M.; Cheung, A.M.; Murad, M.H.; Shoback, D. Pharmacological Management of Osteoporosis in Postmenopausal Women: An Endocrine Society* Clinical Practice Guideline. J. Clin. Endocrinol. Metab. 2019, 104(5), 1595–1622. [Google Scholar] [CrossRef] [PubMed]
- “The 2022 Hormone Therapy Position Statement of The North American Menopause Society” Advisory Panel. The 2022 hormone therapy position statement of The North American Menopause Society. Menopause 2022, 29(7), 767–794. [CrossRef] [PubMed]
- Cauley, J.A.; Robbins, J.; Chen, Z.; Cummings, S.R.; Jackson, R.D.; LaCroix, A.Z.; et al. Women’s Health Initiative Investigators. Effects of estrogen plus progestin on risk of fracture and bone mineral density: the Women’s Health Initiative randomized trial. JAMA 2003, 290(13), 1729–38. [Google Scholar] [CrossRef] [PubMed]
- Black, D.M.; Cummings, S.R.; Karpf, D.B.; Cauley, J.A.; Thompson, D.E.; Nevitt, M.C.; et al. Randomised trial of effect of alendronate on risk of fracture in women with existing vertebral fractures. Fracture Intervention Trial Research Group. Lancet 1996, 348(9041), 1535–41. [Google Scholar] [CrossRef] [PubMed]
- Bone, H.G.; Greenspan, S.L.; McKeever, C.; Bell, N.; Davidson, M.; Downs, R.W.; et al. Alendronate and estrogen effects in postmenopausal women with low bone mineral density. Alendronate/Estrogen Study Group. J. Clin. Endocrinol. Metab. 2000, 85(2), 720–6. [Google Scholar] [PubMed]
- Greenspan, S.L.; Resnick, N.M.; Parker, R.A. Combination therapy with hormone replacement and alendronate for prevention of bone loss in elderly women: a randomized controlled trial. JAMA 2003, 289(19), 2525–33. [Google Scholar] [CrossRef]
- McCloskey, E.V.; Odén, A.; Harvey, N.C.; Leslie, W.D.; Hans, D.; Johansson, H.; et al. A Meta-Analysis of Trabecular Bone Score in Fracture Risk Prediction and Its Relationship to FRAX. J. Bone Min. Res. 2016, 31(5), 940–8. [Google Scholar] [CrossRef] [PubMed]
- Shevroja, E.; Reginster, J.Y.; Lamy, O.; Al-Daghri, N.; Chandran, M.; Demoux-Baiada, A.L.; et al. Update on the clinical use of trabecular bone score (TBS) in the management of osteoporosis: results of an expert group meeting organized by the European Society for Clinical and Economic Aspects of Osteoporosis, Osteoarthritis and Musculoskeletal Diseases (ESCEO), and the International Osteoporosis Foundation (IOF) under the auspices of WHO Collaborating Center for Epidemiology of Musculoskeletal Health and Aging. Osteoporos. Int. 2023, 34(9), 1501–1529. [Google Scholar] [CrossRef] [PubMed]
- Goel, H.; Binkley, N.; Boggild, M.; Chan, W.P.; Leslie, W.D.; McCloskey, E.; et al. Clinical Use of Trabecular Bone Score: The 2023 ISCD Official Positions. J. Clin. Densitom. 2024, 27(1), 101452. [Google Scholar] [CrossRef] [PubMed]
- Krieg, M.A.; Aubry-Rozier, B.; Hans, D.; Leslie, W.D. Manitoba Bone Density Program. Effects of anti-resorptive agents on trabecular bone score (TBS) in older women. Osteoporos. Int. 2013, 24(3), 1073–8. [Google Scholar] [PubMed]
- Papadakis, G.; Hans, D.; Gonzalez-Rodriguez, E.; Vollenweider, P.; Waeber, G.; Marques-Vidal, P.M.; et al. The Benefit of Menopausal Hormone Therapy on Bone Density and Microarchitecture Persists After its Withdrawal. J. Clin. Endocrinol. Metab. 2016, 101(12), 5004–5011. [Google Scholar] [CrossRef] [PubMed]
- Farr, J.N.; Khosla, S.; Miyabara, Y.; Miller, V.M.; Kearns, A.E. Effects of estrogen with micronized progesterone on cortical and trabecular bone mass and microstructure in recently postmenopausal women. J. Clin. Endocrinol. Metab. 2013, 98(2), E249-57. [Google Scholar] [CrossRef] [PubMed]
- Shin, M.S.; Cho, E.H.; Kim, H.Y. Longitudinal Change in Trabecular Bone Score during and after Treatment of Osteoporosis in Postmenopausal Korean Women. J. Bone Metab. 2017, 24(2), 117–124. [Google Scholar] [CrossRef] [PubMed]
- Burghardt, A.J.; Kazakia, G.J.; Sode, M.; de Papp, A.E.; Link, T.M.; Majumdar, S. A longitudinal HR-pQCT study of alendronate treatment in postmenopausal women with low bone density: Relations among density, cortical and trabecular microarchitecture, biomechanics, and bone turnover. J. Bone Min. Res. 2010, 25(12), 2558–71. [Google Scholar] [CrossRef] [PubMed]
- Krohn, K.; Schwartz, E.N.; Chung, Y.S.; Lewiecki, E.M. Dual-energy X-ray Absorptiometry Monitoring with Trabecular Bone Score: 2019 ISCD Official Position. J. Clin. Densitom. 2019, 22(4), 501–505. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Flow diagram of participant selection and follow-up.
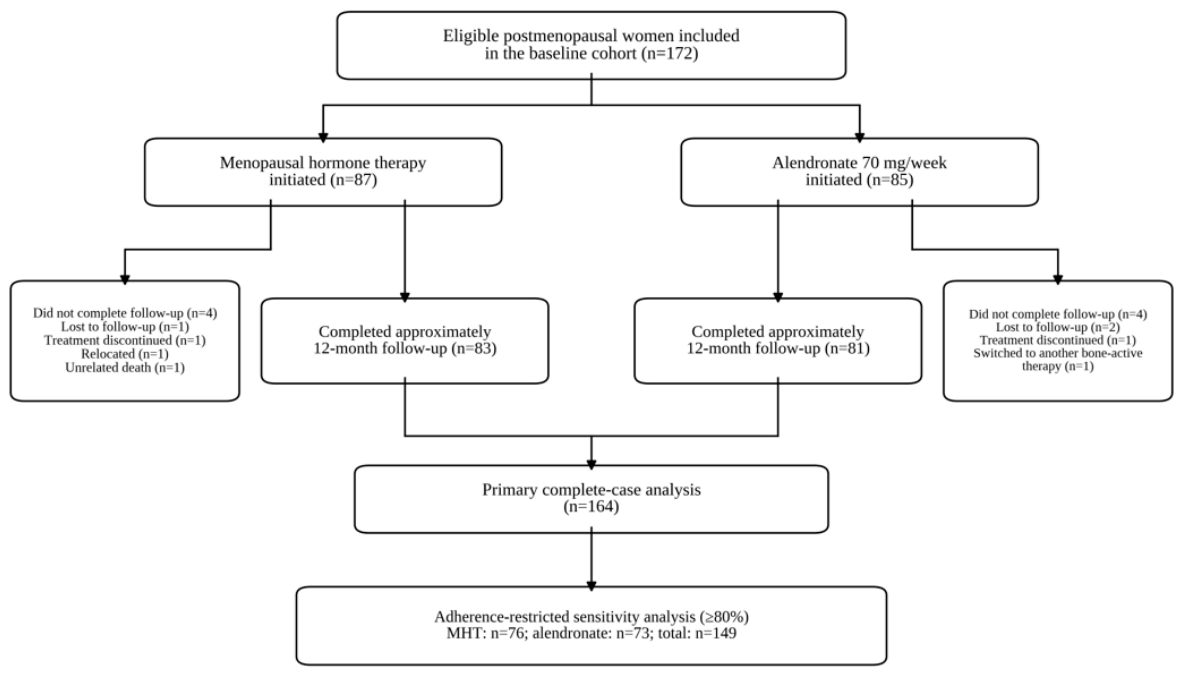

Table 1.
Baseline characteristics and follow-up profile of the study cohort.
| Variable | MHT (n=87) |
Alendronate (n=85) |
P value |
|---|---|---|---|
| Age, years | 57.4 ± 2.7 | 57.4 ± 3.0 | 0.960 |
| Duration of menopause, years | 6.8 ± 2.1 | 6.7 ± 2.1 | 0.768 |
| Body mass index, kg/m2 | 26.7 ± 2.8 | 26.8 ± 2.8 | 0.841 |
| Diabetes mellitus | 11 (12.6) | 12 (14.1) | 0.776 |
| Previous fragility fracture | 9 (10.3) | 11 (12.9) | 0.595 |
| Current smoking | 14 (16.1) | 13 (15.3) | 0.886 |
| Calcium and/or vitamin D supplementation | 69 (79.3) | 70 (82.4) | 0.612 |
| Lumbar spine BMD, g/cm2 | 0.805 ± 0.061 | 0.798 ± 0.058 | 0.471 |
| Femoral neck BMD, g/cm2 | 0.673 ± 0.046 | 0.676 ± 0.047 | 0.620 |
| Total hip BMD, g/cm2 | 0.726 ± 0.053 | 0.725 ± 0.053 | 0.916 |
| Trabecular bone score | 1.256 ± 0.059 | 1.258 ± 0.056 | 0.826 |
| Completed approximately 12-month follow-up | 83 (95.4) | 81 (95.3) | 1.000 |
| Follow-up duration, months | 12.3 (11.8–12.7) | 12.0 (11.7–12.4) | 0.037 |
| Adequate treatment adherence (≥80%) | 76 (91.6) | 73 (90.1) | 0.749 |
Baseline characteristics are reported for all included participants (MHT, n=87; alendronate, n=85). Data are presented as mean ± standard deviation, n (%), or median (interquartile range), as appropriate. P values were calculated using the independent-samples t test, Pearson chi-square test, Fisher’s exact test, or Mann–Whitney U test. Follow-up duration and adequate adherence are reported among participants completing the approximately 12-month evaluation (MHT, n=83; alendronate, n=81). BMD, bone mineral density; MHT, menopausal hormone therapy.
Table 2.
Changes in trabecular bone score and bone mineral density from baseline to approximately 12 months in the complete-case cohort.
Table 2.
Changes in trabecular bone score and bone mineral density from baseline to approximately 12 months in the complete-case cohort.
| Outcome | MHT baseline | MHT 12 months | MHT change | Within-group P | Alendronate baseline | Alendronate 12 months | Alendronate change | Within-group P | Adjusted mean difference at 12 months, MHT − alendronate (95% CI) | P value |
|---|---|---|---|---|---|---|---|---|---|---|
| Trabecular bone score | 1.258 ± 0.058 | 1.260 ± 0.072 | 0.002 ± 0.044 | 0.699 | 1.257 ±0.057 | 1.239 ± 0.070 | −0.018 ± 0.040 | <0.001 | 0.023 (0.010 to 0.036) | <0.001 |
| Lumbar spine BMD, g/cm2 | 0.806 ± 0.061 | 0.820 ± 0.060 | 0.014 ± 0.018 | <0.001 | 0.800 ±0.056 | 0.828 ± 0.056 | 0.028 ± 0.015 | <0.001 | −0.014 (−0.019 to −0.009) | <0.001 |
| Femoral neck BMD, g/cm2 | 0.672 ± 0.046 | 0.678 ± 0.048 | 0.006 ± 0.014 | <0.001 | 0.676 ±0.047 | 0.688 ± 0.048 | 0.012 ± 0.011 | <0.001 | −0.005 (−0.009 to −0.001) | 0.013 |
| Total hip BMD, g/cm2 | 0.725 ± 0.054 | 0.733 ± 0.055 | 0.008 ± 0.013 | <0.001 | 0.725 ±0.053 | 0.740 ± 0.055 | 0.015 ± 0.012 | <0.001 | −0.007 (−0.011 to −0.003) | <0.001 |
Data are presented as mean ± standard deviation. Within-group P values were obtained using the paired-samples t test or Wilcoxon signed-rank test, as appropriate. Adjusted between-group differences were estimated using analysis of covariance, with adjustment for the corresponding baseline outcome, age, duration of menopause, baseline body mass index, diabetes mellitus, previous fragility fracture, current smoking, calcium and/or vitamin D supplementation, and follow-up duration. BMD, bone mineral density; CI, confidence interval; MHT, menopausal hormone therapy; TBS, trabecular bone score. Negative adjusted differences in BMD outcomes indicate greater increases in the alendronate group, whereas a positive adjusted difference in TBS indicates a more favorable outcome in the MHT group.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.