

Submitted:
11 September 2026
Posted:
11 September 2026
You are already at the latest version
Abstract
Zirconia-based ceramics are widely used in fixed prosthodontic restorations owing to their favorable mechanical properties and evolving aesthetic characteristics. However, predicting long-term performance remains challenging because artificial ageing methodologies are highly heterogeneous and existing standards do not fully reflect the diversity of modern zirconia systems, including high-translucency and multilayer materials; variations in experimental conditions, specimen designs, measurement approaches, and reporting practices limit inter-study comparison and quantitative evidence synthesis. This review examines current artificial ageing methodologies for zirconia-based restorations and identifies a fundamental limitation beyond the absence of a universal ageing protocol: the lack of a standardized framework for preserving and exchanging experimental information. To address this, the Minimum Information About a Zirconia Experiment (MIAZE) reporting framework is proposed as a model-neutral, machine-readable structure for documenting experimental observations and associated metadata. MIAZE is a minimal reporting standard that does not require identical experimental protocols, instrumentation, or analytical approaches, but defines the essential information needed to preserve scientific interpretability and enable future dataset reuse. By separating data documentation from subsequent interpretation, MIAZE provides a foundation for reproducibility, independent verification, quantitative meta-analysis, and the application of diverse analytical approaches, shifting the focus from a single universal ageing protocol toward interoperable experimental datasets capable of supporting evolving zirconia materials, methodologies, and computational tools.
Keywords:
zirconia
; fixed prosthodontics
; artificial ageing
; hydrothermal degradation
; thermocycling
; chewing simulation
; low-temperature degradation
; phase transformation
; in vitro testing
1. Introduction
Yttria-stabilised tetragonal zirconia polycrystal (Y-TZP) was introduced into dentistry in the early 2000s and has since become the material of choice for a wide range of fixed prosthodontic restorations, from single crowns to multi-unit fixed dental prostheses (FDPs) [1,2]. Its clinical success is attributable to exceptional flexural strength, fracture toughness via the tetragonal-to-monoclinic (t→m) transformation-toughening mechanism, biocompatibility, and a continuously improving aesthetic potential enabled by successive material generations [3,4]. Long-term clinical follow-up supports the use of tooth-supported zirconia restorations across single crowns and multi-unit fixed dental prostheses [5,6].
A fundamental concern with all Y-TZP formulations is their susceptibility to hydrothermal degradation, also termed low-temperature degradation (LTD) or ageing. In the oral environment, zirconia restorations are continuously exposed to moisture, thermal fluctuations, masticatory forces, and chemical challenges from food, beverages, and saliva. These stressors can drive a spontaneous, surface-initiated t→m phase transformation, accompanied by a ~4–5% volume expansion that generates compressive stresses and microcracking at the surface, progressively roughening the material and diminishing mechanical properties in susceptible compositions [7,8].
In vitro artificial ageing is designed to simulate years of in vivo service within a manageable experimental timeframe. However, zirconia in the specific context of fixed prosthodontics lacks a dedicated, universally accepted ageing protocol. The existing ISO 13356 standard addresses the characterisation of Y-TZP for biomedical applications — originally developed for orthopaedic implants — and specifies hydrothermal ageing at 134 °C, 2 bar, for 5 hours. While this provides a valuable comparative benchmark, its applicability to the complex prosthetic loading environment of the oral cavity is limited: ISO 13356 evaluates a single, fixed hydrothermal condition originally calibrated for orthopaedic-grade 3Y-TZP, and it does not fully account either for the distinct ageing behaviour of contemporary translucent, high-yttria zirconia generations or for the combined thermal, chemical, and mechanical stressors present intraorally [9,10].
This is a narrow, protocol-level limitation, but it is symptomatic of a broader, field-wide problem. The increasing diversity of zirconia materials and artificial ageing methodologies suggests that the principal challenge is not solely the absence of a universal testing protocol, but the inability to consistently preserve, compare, and reuse experimental information generated under heterogeneous conditions. Existing ISO standards define how laboratory testing should be performed, but they lack any mechanism for data standardisation or reporting — the gap this work addresses through the MIAZE framework introduced below. Formal consensus standards are, moreover, structurally unable to keep pace with the rate at which new zirconia generations and commercial formulations reach the market. Compounding this, commercial dental zirconia is produced under proprietary, undisclosed manufacturing parameters; because dopant profiles and sintering technologies are not shared between companies, each product functions as a compositional “black box,” and independent characterisation must rely on empirical benchmarking of the finished material rather than reverse-engineering its formulation [see also Section 2.1].
This methodological gap has led to a proliferation of heterogeneous ageing protocols throughout the dental literature. Because these protocols vary in temperature, pressure, duration, thermocycle number, mechanical loading parameters, chemical agents, specimen geometries, and their combinations, direct inter-study comparisons are extremely challenging [11,12,13,14,15,16,17] — reinforcing the need for the standardised reporting layer proposed in this work (Section 4).
Accordingly, this narrative review systematically analyses the principal artificial ageing methodologies applied to zirconia-based materials in fixed prosthodontics, evaluates their mechanistic rationale and clinical relevance, and identifies the major sources of methodological heterogeneity. Rather than proposing another universal ageing protocol or a replacement for existing ISO standards, this work proposes a structured, machine-readable reporting framework — the Minimum Information About a Zirconia Experiment (MIAZE) — in which experimental observations and metadata are preserved in an open JSON format, independent of the specific protocol used to generate them. By establishing this standardised data infrastructure, experimental datasets generated across different laboratories can be preserved, shared, compared, and independently reanalysed, remaining flexible enough to accommodate the continuous evolution of both experimental protocols and zirconia materials themselves.
2. Material Context and Current Methodologies
2.1. Zirconia Generations and the Commercial “Black Box”
Understanding artificial ageing requires evaluating how zirconia composition and microstructure influence susceptibility to low-temperature degradation. This section summarises the four compositional zirconia classes commonly used in prosthodontics [18,19,20]: conventional 3Y-TZP (first generation), translucent 3Y-TZP (second generation), 5Y-TZP (third generation), and 4Y-TZP (fourth generation), numbered by clinical introduction rather than by yttria content. Increasing yttria content promotes stabilisation of the cubic phase, enhancing translucency and improving resistance to LTD — at the expense of transformation toughening and, consequently, flexural strength. Structural design (monolithic vs. multilayer) is independent of compositional class: any formulation may be manufactured as either.
As yttria rises from 3 to 5 mol%, the cubic-phase fraction increases at the expense of the transformable tetragonal phase that governs both transformation toughening and susceptibility to low-temperature degradation. Figure 1 shows this stabilisation relationship directly: as yttria content rises from 3 to 5 mol%, the cubic-phase fraction increases at the expense of the transformable tetragonal phase that drives both toughening and LTD susceptibility — the compositional axis along which the four generations described below are positioned.
3Y-TZP (First and Second Generation). The original first-generation formulation (3 mol% Y2O3, ~0.25 wt% Al2O3) has the highest proportion of transformable tetragonal phase and the most pronounced LTD susceptibility, historically used as a veneered coping material rather than monolithically [18,21]. Second-generation 3Y-TZP increased translucency by reducing Al2O3 content (~0.05 wt%) and raising sintering temperature, which increases grain size and consequently heightens LTD susceptibility relative to first-generation compositions [22]. Surface treatment (e.g., sandblasting) prior to ageing further alters morphology and residual stress, influencing subsequent degradation kinetics [12,23].
5Y-TZP and 4Y-TZP (Third and Fourth Generation). 5Y-TZP (5 mol% yttria) stabilises more than 50% of the microstructure in the cubic phase, dramatically increasing translucency while diminishing the transformation-toughening mechanism (flexural strength 400–900 MPa) — but yielding substantially greater resistance to hydrothermal ageing [18,24]. Standard autoclave ageing produces negligible t→m conversion in 5Y-TZP, confirming that classical LTD is not a primary clinical concern for this generation [14,25]; optical properties remain similarly stable after prolonged ageing [26,27,28,29]. 4Y-TZP (4 mol% yttria) was developed as a compromise, offering intermediate translucency, mechanical performance, and hydrothermal ageing resistance between 3Y-TZP and 5Y-TZP [13], allowing clinicians to balance aesthetics with durability where high-strength requirements preclude 5Y-TZP.
Multilayer Zirconia. Contemporary multilayer systems combine layers of differing yttria content — typically 3Y-TZP cervically/occlusally to 5Y-TZP incisally — to simultaneously optimise strength and aesthetics. Ageing behaviour is layer-dependent: 3Y-TZP and transitional layers undergo meaningful t→m transformation upon hydrothermal ageing, while 4Y-TZP/5Y-TZP layers remain largely resistant, even after extended autoclave exposure [30,31,32]. This heterogeneous, layer-dependent response within a single restoration has direct implications for how multilayer systems should be aged and characterised in laboratory studies [16,17,33].
Figure 2 makes explicit that these two axes are independent: any of the four compositional classes above may be manufactured as either a homogeneous monolithic disc or a graded multilayer disc, which is precisely why a single generation label is not sufficient to predict a restoration’s ageing behaviour once structural design is also in play.
Implication for benchmarking. Because manufacturing parameters, dopant profiles, and sintering technologies are not disclosed by manufacturers, commercial zirconia discs behave as compositional black boxes despite belonging to a known generation class. Materials nominally in the same generation can therefore exhibit materially different ageing susceptibility depending on undisclosed processing variables. This problem compounds further in multilayer systems, where a single disc contains several compositionally distinct, independently ageing zones (see Multilayer Zirconia, above): black-box opacity at the product level and layer-level compositional heterogeneity together mean that benchmarking cannot treat a restoration as a single material. What is required is a reporting approach flexible enough to document each layer or material zone as its own discrete experimental unit, rather than collapsing a multilayer specimen into one whole-restoration data point. This reinforces that meaningful comparison across commercial products must rely on standardised empirical benchmarking of finished materials, at the resolution of the individual layer where relevant — which is only possible if the resulting data is reported in a consistent, reusable format (see Section 4).
2.2. Survey of Ageing Protocols and Data-Representation Gaps
Four principal categories of artificial ageing are applied to dental zirconia, each targeting distinct degradation pathways (Table 1, Figure 3):
Figure 3 maps these four domains schematically around a central restoration, with a dashed overlay marking where combined, multi-stage protocols (discussed below) target more than one domain simultaneously; the four categories are detailed in turn here.
Hydrothermal Ageing (Autoclave). The principal method for evaluating LTD, exposing specimens to saturated steam to induce surface-to-bulk t→m transformation. While ISO 13356:2015 specifies benchmark conditions (134 °C, 2 bar, 5 hours), reported parameters vary considerably (110–140 °C; 3–64 hours), and extreme temperature acceleration can misrepresent oral kinetics, potentially overestimating degradation in contemporary high-yttria zirconia [34,35].
Thermocycling. Simulates dietary temperature fluctuations (typically 5–55 °C) to assess thermal fatigue, primarily at bonded interfaces since bulk zirconia shows minimal structural change. Protocols in the dental literature are unstandardised, with cycle numbers ranging from 600 to 50,000 [36,37,38,39].
Mechanical Ageing (Chewing Simulation). Replicates cyclic fatigue and moisture-assisted subcritical crack growth. Common protocols use 1.2 million cycles (≈5 years simulated function) at 50–200 N, but significant variability exists in load magnitude, antagonist material, and layer-specific yttria content across studies [40,41,42,43].
Chemical and Photoageing. Chemical immersion (e.g., 4% acetic acid, HCl) simulates acidic challenge via kinetic mechanisms distinct from hydrothermal ageing; UV photoageing primarily assesses extrinsic colour/cement stability rather than intrinsic structural longevity [44,45,46]. Combined thermo-mechanical or multi-stage protocols introduce further methodological variables.
The Fragmentation Gap. A programmatic analysis of PubMed records from 2016–2026 reveals a significant fragmentation gap in zirconia research (Figure 4): while formal ISO-standard investigations show static publication trends, the volume of studies employing heterogeneous, custom experimental designs is rapidly increasing. A substantial portion of this literature routinely omits critical measurement metadata (instrumentation, calibration) and explicit experimental increments (applied time, load steps), limiting reusability and aggregation.
The heterogeneity is not confined to protocol selection — it extends through every stage of experimental design and outcome reporting:
- Time–temperature equivalency remains contested: the widely used > conversion of 1 hour at 134 °C ≈ 3–4 years in vivo [8] > conflicts with real-time ageing data suggesting a factor closer to > 1 hour ≈ 1 year [47] — a two- to fourfold discrepancy that > materially changes the clinical interpretation of identical > experiments. Autoclave chamber volume, pressure regulation, > heating ramp rate, and water volume are similarly > under-standardised across laboratories.
- Generation-specific susceptibility means a single hydrothermal > protocol cannot meaningfully stress both 3Y-TZP and 5Y-TZP: > standard 5-hour ageing effectively challenges 3Y-TZP but barely > perturbs 5Y-TZP, risking the false impression that > high-translucency zirconia is inherently indestructible. > Multilayer systems compound this, as a single whole-restoration > protocol cannot represent the appropriate stress for > compositionally distinct layers within the same disc [30,31].
- Thermocycling parameters span 600–50,000 cycles, 3–60 second > dwell times, and 5–55 °C to 5–75 °C ranges — a heterogeneity > explicitly recognised in landmark reviews as rendering inter-study > comparison essentially impossible [48].
- Chewing simulation variables — load magnitude, frequency, > antagonist material, loading geometry — vary substantially, and > the reference convention of 1.2×10⁶ cycles ≈ 5 years is itself > only an approximation, since individual masticatory cycle number > per year is estimated to range 200,000–1,000,000.
- Outcome reporting is as heterogeneous as protocol selection: phase > transformation is quantified via different XRD methods with > differing reference intensities; flexural strength testing employs > three-point, four-point, and biaxial configurations with different > span lengths and loading rates; colour assessment uses different > illuminants, apertures, and formulae (ΔE* CIE 1976 vs. ΔE00 CIE > 2000).
Because of this compounding heterogeneity — spanning protocol selection, environmental control, and outcome quantification simultaneously — a quantitative meta-analysis was not feasible for the present review. This is not merely an inconvenience for narrative synthesis: it is the central symptom that motivates the diagnosis and proposal developed in the remainder of this work.
3. Core Gaps and Root-Cause Analysis
A persistent limitation across the literature is the absence of a dedicated standard specifically addressing the artificial ageing of zirconia in fixed prosthodontics. Existing standards, such as ISO 13356, were originally developed for general biomedical applications and fail to capture the mechanical loading conditions, compositional complexity, or clinical heterogeneity of modern dental systems, particularly multilayer and high-translucency materials. This regulatory vacuum has produced a landscape dominated by proprietary, non-standardised protocols: because dental research currently operates in isolated silos, experimental data are frequently trapped within unique, study-specific formats — typically free-text descriptions and static, non-machine-readable summary tables — often reporting only condensed outcomes rather than the underlying material baseline, experimental increments, or response observations needed for independent reuse. This is a distinct problem from the manufacturer-level opacity discussed in Section 2.1: there, the barrier is undisclosed composition; here, the barrier is how researchers who do have full access to their own raw data choose to report it.
The same disconnect reappears one level up, between the laboratory and the clinic. Validating in vitro ageing protocols requires correlating laboratory-derived kinetic data with the documented service history of clinically retrieved zirconia restorations — yet this correlation is only as good as the resolution at which the original laboratory data was captured. Where studies report only pass/fail outcomes or condensed summary statistics, there is no way to retrospectively align them with retrieval findings, regardless of how good the underlying experiment was. This is not a shortage of ageing studies; it is a shortage of ageing data preserved at a resolution fine enough to be reused for a question the original authors did not anticipate.
Table 2 illustrates what this correlation could look like in practice, once laboratory data is captured at sufficient resolution — but the matrix itself presupposes the very reporting granularity that current summary-outcome-only publications do not provide.
Both symptoms — the absence of a fixed-prosthodontic-specific standard, and the lab-to-clinic disconnect — trace back to a single conflation. The field has treated standardising how data is reported and standardising how data is interpreted as though they were the same problem, and has consistently tried to solve the reporting gap by proposing yet another testing protocol. But no protocol, however carefully designed, can be adopted fast enough: formal ISO consensus mechanisms operate on a timescale of years, while commercial zirconia generations and formulations turn over continuously. Chasing protocol consensus is therefore chasing a moving target. The true barrier to comparable, reusable, clinically-correlatable zirconia data is not the absence of the right analytical method — it is structural: the absence of a common format in which any method’s inputs and outputs can be recorded, regardless of which protocol produced them. It is this specific structural void — not a shortage of candidate testing protocols — that the MIAZE framework proposed below is designed to fill.
Table 3 makes this conflation concrete: for each recurring methodological limitation in the ageing literature — heterogeneous time–temperature assumptions, generation-specific susceptibility, inconsistent outcome quantification — a corresponding analytical approach already exists in principle, but remains inapplicable in practice because the underlying raw observations were never captured in a form that supports it. Section 5.1 returns to this table to show what becomes possible once that capture problem is solved.
This reframing is the basis for the Minimum Information About a Zirconia Experiment (MIAZE) framework, proposed here as a foundational data infrastructure layer rather than a competing testing protocol. MIAZE is not designed to resolve which ageing protocol, time–temperature conversion factor, or outcome metric is “correct” — it is designed so that whichever choices a given study makes, the resulting observations are captured in a form that remains interoperable with every other study’s choices. By prioritising semantic interoperability over protocol uniformity, MIAZE allows studies that share an objective but differ in experimental design to still be mapped against one another.
Critically, MIAZE functions as a structural prerequisite for interoperability, not an analytical method in itself. It embeds no assumptions about degradation mechanisms, kinetic models, or statistical approach. Instead, it defines a clean, machine-readable dataset boundary below which raw observations are recorded, and above which any analytical toolset — kinetic modelling, statistical regression, machine learning, or direct clinical-retrieval correlation — can operate independently, without being constrained or presupposed by the reporting layer itself. This separation is what makes the framework proposed in the remainder of this work fundamentally different from a new ageing protocol: it does not ask the field to agree on how to test zirconia, only on how to record what was done and what was observed.
4. The MIAZE Framework
MIAZE — the Minimum Information About a Zirconia Experiment — is a minimal, model-neutral reporting standard for zirconia-based experimental studies in fixed prosthodontics. Its purpose is to preserve the scientific interpretability, reproducibility, and future reusability of experimental datasets, regardless of which ageing protocol, instrumentation, or analytical method produced them. Critically, MIAZE does not require researchers to adopt identical experimental protocols or analytical approaches; it provides a standardised structure for documenting what was done and what was observed, allowing heterogeneous studies to remain comparable while preserving the flexibility each research group needs for its own objectives.
MIAZE specifies data reporting only. It does not prescribe analytical frameworks, mathematical models, or interpretation strategies — those remain independent and may be selected according to the dataset and the scientific question at hand. This separation is enforced by four core reporting principles: observation primacy (only directly measured observations and metadata are reported; derived analytical parameters are excluded), model neutrality (the structure is independent of any specific kinetic, statistical, or machine-learning model), interoperability (data are encoded in structured key–value format — JSON or equivalent — for computational reuse), and complete metadata context (experimental conditions, instrumentation, and specimen provenance are fully documented). Together, these principles align MIAZE with the broader FAIR data principles (findable, accessible, interoperable, reusable), extending zirconia reporting beyond static publication toward long-term, computationally accessible datasets.
A MIAZE-compliant dataset is built from four minimum reporting elements, summarised in Table 4: a material baseline (manufacturer, batch identifier, yttria content, specimen design, initial phase composition), the experimental increments applied (independent variables such as time, temperature, chemical environment, or load cycles), the response observations directly measured (phase composition, mechanical strength, optical properties, or equivalent outcomes), and the measurement metadata describing how those observations were acquired (instrumentation, acquisition parameters, resolution, calibration, uncertainty). JSON was selected as the initial implementation format because it is open, platform-independent, human-readable, and machine-processable, and because schemas expressed in JSON can be programmatically validated — for example using standard schema-validation libraries — ensuring datasets conform to the standard before they are ever reused. The full schema definition, validation rules, and a worked example are provided in the Technical Annex (Appendices A–C); this section presents the conceptual architecture only, since the mechanical detail is not required to understand what MIAZE enables.
5. Downstream Capabilities Enabled by MIAZE
5.1. Data Synthesis and Meta-Analysis
The immediate consequence of separating data reporting from data interpretation is that the same MIAZE-compliant dataset can support multiple, independently chosen analytical approaches without requiring the underlying data to be restructured for each one. Table 3 (Section 3) already illustrated this: the methodological limitations that currently fragment the ageing literature — heterogeneous time–temperature assumptions, generation-specific susceptibility, inconsistent outcome quantification — map onto a corresponding set of analytical strategies that only become usable once the raw observations are captured completely and consistently.
Rather than relying on fixed analytical paradigms or speculative time-based extrapolation alone, structured, machine-readable datasets enable several complementary directions. Reference-based normalisation can contextualise material performance against a defined benchmark (e.g., 3Y-TZP) to reduce inter-laboratory variability, provided the reference choice is reported explicitly and independently of the data format itself. Methodological harmonisation — controlled specimen geometries, or parallel testing across hydrothermal, mechanical, and chemical stressors — improves comparability without forcing every laboratory onto a single protocol. And quantitative reporting of degradation behaviour, using continuous response variables rather than qualitative pass/fail outcomes, allows the same dataset to be interpreted through classical kinetic modelling, statistical regression, or data-driven machine-learning techniques, depending on the research question (Table 5). None of these approaches requires modification to the underlying MIAZE structure; they are simply different lenses applied above the reporting layer.
This is also the basis on which MIAZE datasets become viable inputs for machine-learning applications specifically: consistent, complete, per-experiment records of increments and response observations are precisely the structured input format that model training and testing require, without MIAZE itself dictating which model is appropriate. As harmonised datasets accumulate across laboratories, the same infrastructure that enables manual meta-analysis today extends naturally to larger-scale, computational data-mining tomorrow.
5.2. Clinical Decision Tree and Patient Selection (Proof of Concept)
The preceding sections establish MIAZE as data infrastructure; this section demonstrates, in a single worked example, why that infrastructure matters clinically and not only analytically. Zirconia’s compositional generations, structural designs, and ageing behaviour — surveyed in Section 2 — are, individually, well-characterised. What clinicians actually need, however, is a unified interpretation of how composition, microstructure, and ageing behaviour collectively determine material suitability for a specific patient and a specific restoration, since patient needs are governed in large part by the fundamental trade-off between aesthetic translucency and mechanical performance that yttria content controls (Figure 6).
Figure 6 sets this trade-off alongside two further variables — the restoration’s anatomical position and its functional load-bearing demand — so that material choice can be reasoned through all three axes together, rather than on translucency versus strength alone.
Figure 7 presents a clinical decision tree that consolidates these material characteristics into an evidence-based workflow, assisting clinicians in selecting the appropriate zirconia generation and structural design by aligning material properties with clinical requirements — anatomical position, aesthetic demand, and functional load. This tool is only as reliable as the underlying material data feeding it: standardised, MIAZE-compliant reporting of generation-specific ageing behaviour is what allows such a decision tree to be built on comparable evidence across products and studies, rather than on a patchwork of incompatible summary claims.
Looking forward, it is worth being precise about what MIAZE does and does not claim. MIAZE is a data-delivery layer, not a clinical tool, an analytical model, or a machine-learning system. Its role is analogous to the standardised array and table formats (e.g., those underlying Python’s scikit-learn or pandas ecosystems) that have become foundational to open-source scientific computing: such formats do not themselves classify, predict, or diagnose anything — they simply guarantee that data produced by one group can be consumed, without reformatting, by any downstream tool a different group chooses to build, whether that tool is a plotting script, a kinetic-model fitter, a statistical test, or a machine-learning classifier. MIAZE aims to occupy the same position for zirconia ageing data: by fixing the structure of material_baseline, experimental_increments, response_observations, and measurement_metadata, it gives future independent researchers and software developers a stable, predictable input format to build against.
Whether that eventually includes clinical decision-support software that cross-references patient-specific risk factors (e.g., bruxism, acidic dietary exposure, oral hygiene) against harmonised material performance profiles is, at this stage, an open question for the field to pursue — not a capability this paper proposes, demonstrates, or claims to deliver. No such tool exists today, and building one is explicitly outside MIAZE’s scope; MIAZE’s only claim is that, if such a tool is built, standardised data will be available for it to consume.
In summary, clinical material selection is best served by a holistic, evidence-based workflow rather than a focus on isolated material properties in isolation. The patient-centred scheme and clinical decision tree together demonstrate that zirconia performance is a dynamic outcome of restoration design, compositional class, and site-specific functional demand — and that reconciling the trade-off between aesthetic translucency and mechanical reliability depends on the same standardised, comparable data that Section 4 and Section 5a establish as the paper’s central proposal.
6. Conclusions and Future Work
Artificial ageing of zirconia-based materials in fixed prosthodontics currently relies on a fragmented spectrum of methodologies, each constrained by mechanistic limitations and uncertain clinical correlations. The widespread reliance on hydrothermal ageing as the principal evaluation method for 3Y-TZP is increasingly inadequate for newer translucent 4Y-TZP and 5Y-TZP generations, which exhibit substantially different degradation behaviour, and the unresolved discrepancy between competing time–temperature equivalency factors illustrates the limits of estimating clinical longevity through temporal extrapolation alone.
As established throughout this review, however, the central obstacle is not primarily a shortage of ageing protocols — the field already has more protocols than it can compare. Rather than relying on disputed service-year conversions, future studies would benefit from emphasising experimentally observed degradation behaviour, supported by transparent and reproducible reporting of experimental conditions and measurements. Standardised reporting through the Minimum Information About a Zirconia Experiment (MIAZE) framework provides the model-neutral, machine-readable structure that makes this possible: by defining the structure, completeness, and interoperability of reported observations without prescribing the analytical methods used for subsequent interpretation, MIAZE resolves the reporting/interpretation conflation diagnosed — not by proposing a competing protocol, but by removing the need to agree on one before data can be meaningfully compared.
As zirconia materials and analytical technologies continue to evolve, preservation of structured experimental information may become as important as the development of new testing methodologies themselves. Once standardised datasets are available, multiple analytical approaches — kinetic modelling, statistical regression, probabilistic analysis, or data-driven computational methods — may be applied according to the research objective and dataset structure, exactly as demonstrated in Section 5. No single analytical approach is universally required; analytical selection should remain dependent on the scientific question, the characteristics of the dataset, and the assumptions of the selected model. Other ageing modalities — thermocycling, chewing simulation, chemical immersion — remain valuable complementary approaches but continue to suffer from substantial methodological heterogeneity; greater harmonisation of protocols, specimen characterisation, and outcome reporting would substantially improve inter-study comparability and future evidence synthesis.
Future research should therefore prioritise: generation-specific ageing protocols that reflect the differing susceptibilities of 3Y-TZP, 4Y-TZP, 5Y-TZP, and multilayer zirconia systems; comprehensive, machine-readable reporting of experimental observations and metadata through standardised frameworks such as MIAZE; transparent reporting of sufficient raw experimental data to enable independent post-hoc analyses using diverse analytical methodologies; continued investigation of normalisation strategies, including reference materials such as high-performance 3Y-TZP, to improve cross-study comparability where appropriate; and long-term validation through clinical retrieval studies capable of linking laboratory observations with real-world material performance.
Until dedicated, generation-specific standards become available, researchers are encouraged to employ sufficiently demanding ageing protocols — including extended hydrothermal exposure where scientifically justified, combined with complementary mechanical and environmental challenges — while placing emphasis on transparent reporting of experimentally observed material behaviour rather than uncertain predictions of clinical service life based solely on disputed temporal equivalency factors. Such an approach provides a robust foundation for reproducible research, future meta-analysis, and the continued development of analytical strategies for understanding zirconia ageing across evolving material generations. The central challenge in zirconia ageing research is therefore not solely the development of additional protocols, but the preservation of experimental information in a structure that allows meaningful comparison across evolving materials, methodologies, and future analytical approaches — the structural prerequisite this review has proposed MIAZE to provide.
Supplementary Materials
The following supporting information can be downloaded at the website of this paper posted on Preprints.org. Technical Annex (Appendices A–C), containing the formal MIAZE schema, a Python validation function, and a worked MIAZE-compliant JSON payload.
Author Contributions
Conceptualization, M.B., M.Ž. and M.J.; methodology, M.B. and M.Ž.; software, M.Ž.; validation, M.B. and M.Ž.; formal analysis, M.B.; investigation, M.B.; data curation, M.B. and M.Ž.; writing—original draft preparation, M.B.; writing—review and editing, M.B., M.Ž. and M.J.; visualization, M.B.; supervision, M.J.; project administration, M.J. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new experimental datasets were generated in this study. The MIAZE schema, a Python validation function, and an illustrative JSON payload are provided in the Supplementary Materials.
Acknowledgments
During the preparation of this manuscript, the authors used Claude (Anthropic) to assist with language editing and manuscript preparation. The authors reviewed and edited the output and take full responsibility for the content of this publication.
Conflicts of Interest
M.J. and M.Ž. are Guest Editors of the Special Issue “Advances in Zirconia-Based Dental Materials” of the Journal of Functional Biomaterials. To avoid any conflict of interest, they were not involved in the editorial handling or peer-review decisions concerning this manuscript, which was managed independently by the journal. The authors declare no other conflict of interest.
References
- Pjetursson, B.E.; Sailer, I.; Zwahlen, M.; Hämmerle, C.H.F. A systematic review of the survival and complication rates of all-ceramic and metal-ceramic reconstructions after an observation period of at least 3 years. Part I: Single crowns. Clin. Oral Implant. Res. 2007, 18 (Suppl. 3), 73–85. [Google Scholar] [CrossRef] [PubMed]
- Sulaiman, T.A. Materials in digital dentistry—a review. J. Esthet. Restor. Dent. 2020, 32, 171–181. [Google Scholar] [CrossRef] [PubMed]
- Piconi, C.; Maccauro, G. Zirconia as a ceramic biomaterial. Biomaterials 1999, 20, 1–25. [Google Scholar] [CrossRef] [PubMed]
- Manicone, P.F.; Rossi Iommetti, P.; Raffaelli, L. An overview of zirconia ceramics: Basic properties and clinical applications. J. Dent. 2007, 35, 819–826. [Google Scholar] [CrossRef] [PubMed]
- Sailer, I.; Fehér, A.; Filser, F.; Gauckler, L.J.; Lüthy, H.; Hämmerle, C.H. Five-year clinical results of zirconia frameworks for posterior fixed partial dentures. Int. J. Prosthodont. 2007, 20, 383–388. [Google Scholar] [PubMed]
- Sailer, I.; Makarov, N.A.; Thoma, D.S.; Zwahlen, M.; Pjetursson, B.E. All-ceramic or metal-ceramic tooth-supported fixed dental prostheses (FDPs)? A systematic review of the survival and complication rates. Part I: Single crowns (SCs). Dent. Mater. 2015, 31, 603–623. [Google Scholar] [CrossRef] [PubMed]
- Chevalier, J.; Gremillard, L.; Virkar, A.V.; Clarke, D.R. The tetragonal-monoclinic transformation in zirconia: Lessons learned and future trends. J. Am. Ceram. Soc. 2009, 92, 1901–1920. [Google Scholar] [CrossRef]
- Chevalier, J. What future for zirconia as a biomaterial? Biomaterials 2006, 27, 535–543. [Google Scholar] [CrossRef] [PubMed]
- Sanon, C.; Chevalier, J.; Douillard, T.; Cattani-Lorente, M.; Scherrer, S.S.; Gremillard, L. A new testing protocol for zirconia dental implants. Dent. Mater. 2015, 31, 15–25. [Google Scholar] [CrossRef] [PubMed]
- Lughi, V.; Sergo, V. Low temperature degradation—aging—of zirconia: A critical review of the relevant aspects in dentistry. Dent. Mater. 2010, 26, 807–820. [Google Scholar] [CrossRef] [PubMed]
- Hajhamid, B.; Bozec, L.; Tenenbaum, H.; De Souza, G.; Somogyi-Ganss, E. Effect of artificial aging on optical properties and crystalline structure of high-translucency zirconia. J. Prosthodont. 2024, 33, 61–69. [Google Scholar] [CrossRef] [PubMed]
- Jakovac, M.; Klaser, T.; Radatović, B.; Bafti, A.; Skoko, Ž.; Pavić, L.; Žić, M. Impact of sandblasting on morphology, structure and conductivity of zirconia dental ceramics material. Materials 2021, 14, 2834. [Google Scholar] [CrossRef] [PubMed]
- Jakovac, M.; Klaser, T.; Bafti, A.; Skoko, Ž.; Pavić, L.; Žić, M. The effect of Y3+ addition on morphology, structure, and electrical properties of yttria-stabilized tetragonal zirconia dental materials. Materials 2022, 15, 1800. [Google Scholar] [CrossRef] [PubMed]
- Çelik, S.Ç.; Çakırbay Tanış, M. Effect of hydrothermal aging on mechanical and microstructural properties of zirconia ceramics. Nanomaterials 2025, 15, 1669. [Google Scholar] [CrossRef] [PubMed]
- Hjerppe, J.; Vallittu, P.K.; Fröberg, K.; Lassila, L.V. Effect of sintering time on biaxial strength of zirconium dioxide. Dent. Mater. 2009, 25, 166–171. [Google Scholar] [CrossRef] [PubMed]
- Labetić, A.; Klaser, T.; Skoko, Ž.; Jakovac, M.; Žić, M. Flexural strength and morphological study of different multilayer zirconia dental materials. Materials 2024, 17, 1143. [Google Scholar] [CrossRef] [PubMed]
- Labetić, A.; Klaser, T.; Skoko, Ž.; Jakovac, M.; Žić, M. Surface hardness of polished dental zirconia: influence of polishing and yttria content on morphology, phase composition, and microhardness. Materials 2025, 18, 3380. [Google Scholar] [CrossRef] [PubMed]
- Kongkiatkamon, S.; Rokaya, D.; Kengtanyakich, S.; Peampring, C. Current classification of zirconia in dentistry: An updated review. PeerJ 2023, 11, e15669. [Google Scholar] [CrossRef] [PubMed]
- Denry, I.; Kelly, J.R. State of the art of zirconia for dental applications. Dent. Mater. 2008, 24, 299–307. [Google Scholar] [CrossRef] [PubMed]
- Gracis, S.; Thompson, V.P.; Ferencz, J.L.; Silva, N.R.F.A.; Bonfante, E.A. A new classification system for all-ceramic and ceramic-like restorative materials. Int. J. Prosthodont. 2015, 28, 227–235. [Google Scholar] [CrossRef] [PubMed]
- Zhang, Y.; Lawn, B.R. Novel zirconia materials in dentistry. J. Dent. Res. 2018, 97, 140–147. [Google Scholar] [CrossRef] [PubMed]
- Stawarczyk, B.; Özcan, M.; Hallmann, L.; Ender, A.; Mehl, A.; Hämmerle, C.H.F. The effect of zirconia sintering temperature on flexural strength, grain size, and contrast ratio. Clin. Oral Investig. 2013, 17, 269–274. [Google Scholar] [CrossRef] [PubMed]
- Sulaiman, T.A.; Abdulmajeed, A.A.; Shahramian, K.; Lassila, L. Effect of different treatments on the flexural strength of fully versus partially stabilized monolithic zirconia. J. Prosthet. Dent. 2017, 118, 216–220. [Google Scholar] [CrossRef] [PubMed]
- Raza, S.H.; Khan, A.S.; Chaudhry, A.A. Effect of artificial ageing on optical properties and mechanical strength of high-translucency zirconia: A systematic review and meta-analysis. Int. J. Dent. 2025, 2025, 6617381. [Google Scholar]
- Mešić, K.; Majnarić, I.; Obhođaš, J.; Baršić, G.; Mehulić, K. The effect of aging on composition and surface of translucent zirconia ceramic. Acta Stomatol. Croat. 2020, 54, 356–367. [Google Scholar] [CrossRef] [PubMed]
- Mešić, K.; Majnarić, I.; Mehulić, K. Effect of aging on the microstructure and optical properties of translucent ZrO2 ceramics. Acta Stomatol. Croat. 2021, 55, 114–128. [Google Scholar] [CrossRef] [PubMed]
- Zhang, C.Y.; Agingu, C.; Tsoi, J.K.H.; Yu, H. Effects of aging on the color and translucency of monolithic translucent Y-TZP ceramics: A systematic review and meta-analysis of in vitro studies. BioMed Res. Int. 2021, 2021, 8875023. [Google Scholar] [CrossRef] [PubMed]
- Lümkemann, N.; Stawarczyk, B. Impact of hydrothermal aging on the light transmittance and flexural strength of colored yttria-stabilized zirconia materials of different formulations. J. Prosthet. Dent. 2021, 125, 518–526. [Google Scholar] [CrossRef] [PubMed]
- Yang, F.; Zhou, Z.; Song, X.; Guo, H.; Zhang, Z. Effect of hydrothermal aging on color stability and translucency of two zirconia generations compared to lithium disilicate ceramics. J. Esthet. Restor. Dent. 2024, 36, 1488–1497. [Google Scholar]
- Pöppel, M.L.; Rosentritt, M.; Sturm, R.; Beuer, F.; Hey, J.; Schmid, A.; Schmidt, F. Fracture load and fracture patterns of monolithic three-unit anterior fixed dental prostheses after in vitro artificial aging: A comparison between color-gradient and strength-gradient multilayer zirconia materials with varying yttria content. J. Clin. Med. 2022, 11, 4982. [Google Scholar] [CrossRef] [PubMed]
- Kim, D.Y.; Kim, J.H.; Kim, H.Y.; Kim, W.C. Changes in the properties of different zones in multilayered translucent zirconia used in monolithic restorations during aging process. J. Funct. Biomater. 2025, 16, 96. [Google Scholar] [CrossRef] [PubMed]
- Li, H.; Liang, Y.; Zheng, G.; Yue, L. Effect of low-temperature degradation on the fatigue performance of dental strength-gradient multilayered zirconia restorations. Dent. Mater. 2024, 40, 690–698. [Google Scholar]
- Kim, H.-S.; Kim, J.-H.; Kim, W.-C.; Kim, J.-H. Changes in the flexural strength and surface characteristics of different zones of multilayered translucent zirconia during aging process. J. Mater. Sci. Mater. Med. 2025, 36, 78. [Google Scholar] [CrossRef] [PubMed]
- Yang, F.; Zhao, Z.; Song, X.; Guo, H.; Zhang, Z. Simulated oral environment affects zirconia aging and mechanical strength. J. Mech. Behav. Biomed. Mater. 2025, 162, 106615. [Google Scholar] [CrossRef] [PubMed]
- Flinn, B.D.; deGroot, D.A.; Mancl, L.A.; Raigrodski, A.J. Accelerated aging characteristics of three yttria-stabilized tetragonal zirconia polycrystalline dental materials. J. Prosthet. Dent. 2012, 108, 223–230. [Google Scholar] [CrossRef] [PubMed]
- Lüthy, H.; Loeffel, O.; Hämmerle, C.H.F. Effect of thermocycling on bond strength of luting cements to zirconia ceramic. Dent. Mater. 2006, 22, 195–200. [Google Scholar] [CrossRef] [PubMed]
- Gale, M.S.; Darvell, B.W. In vivo validation of the historical in vitro thermocycling temperature range for dental materials testing. J. Dent. Res. 2004, 83, 654–658. [Google Scholar]
- Yenisey, M.; Dede, D.Ö. Effect of thermocycling on microhardness and surface roughness of two zirconia reinforced lithium silicate glass-ceramics. Eur. J. Dent. 2021, 15, 449–455. [Google Scholar]
- Morresi, A.L.; D’Amario, M.; Capogreco, M.; Gatto, R.; Marzo, G.; D’Arcangelo, C.; Monaco, A. Thermal cycling for restorative materials: Does a standardized protocol exist in laboratory testing? A literature review. J. Mech. Behav. Biomed. Mater. 2014, 29, 295–308. [Google Scholar] [CrossRef] [PubMed]
- Abutaleb, A.S.; Al-Qarni, F.D.; Gad, M.M. Influence of the preparation design and artificial aging on the fracture resistance of monolithic zirconia crowns. Biomed. Res. Int. 2021, 2021, 6690259. [Google Scholar]
- Ziębowicz, A.; Oßwald, B.; Kern, F.; Schwan, W. Effect of simulated mastication on structural stability of prosthetic zirconia material after thermocycling aging. Materials 2023, 16, 1171. [Google Scholar] [CrossRef] [PubMed]
- Rosentritt, M.; Behr, M.; Gebhard, R.; Handel, G. Influence of stress simulation parameters on the fracture strength of all-ceramic fixed-partial dentures. Dent. Mater. 2006, 22, 176–182. [Google Scholar] [CrossRef] [PubMed]
- Preis, V.; Behr, M.; Hahnel, S.; Handel, G.; Rosentritt, M. In vitro failure and fracture resistance of veneered and full-contour zirconia restorations. J. Dent. 2012, 40, 921–928. [Google Scholar] [CrossRef] [PubMed]
- Taşın, S.; Celik, G.; İsmatullaev, A.; Usumez, A. The effect of artificial accelerated aging on the color stability, microhardness, and surface roughness of different dental laminate veneer materials. J. Esthet. Restor. Dent. 2022, 34, 405–411. [Google Scholar] [CrossRef] [PubMed]
- Kim, H.J.; Park, J.Y. Evaluation of feasibility on dental zirconia—accelerated aging test by chemical immersion method. J. Funct. Biomater. 2023, 14, 587. [Google Scholar]
- Kilinc, H.; Turgut, S. Optical behaviors of esthetic CAD-CAM restorations after different surface finishing and polishing procedures and UV aging: An in vitro study. J. Prosthet. Dent. 2018, 120, 107–113. [Google Scholar] [CrossRef] [PubMed]
- Keuper, M.; Berthold, C.; Nickel, K.G. Long-time aging in 3 mol.% yttria-stabilized tetragonal zirconia polycrystals at human body temperature. Acta Biomater. 2014, 10, 951–959. [Google Scholar] [CrossRef] [PubMed]
- Gale, M.S.; Darvell, B.W. Thermal cycling procedures for laboratory testing of dental restorations. J. Dent. 1999, 27, 89–99. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Schematic phase composition of dental zirconia as a function of yttria content.
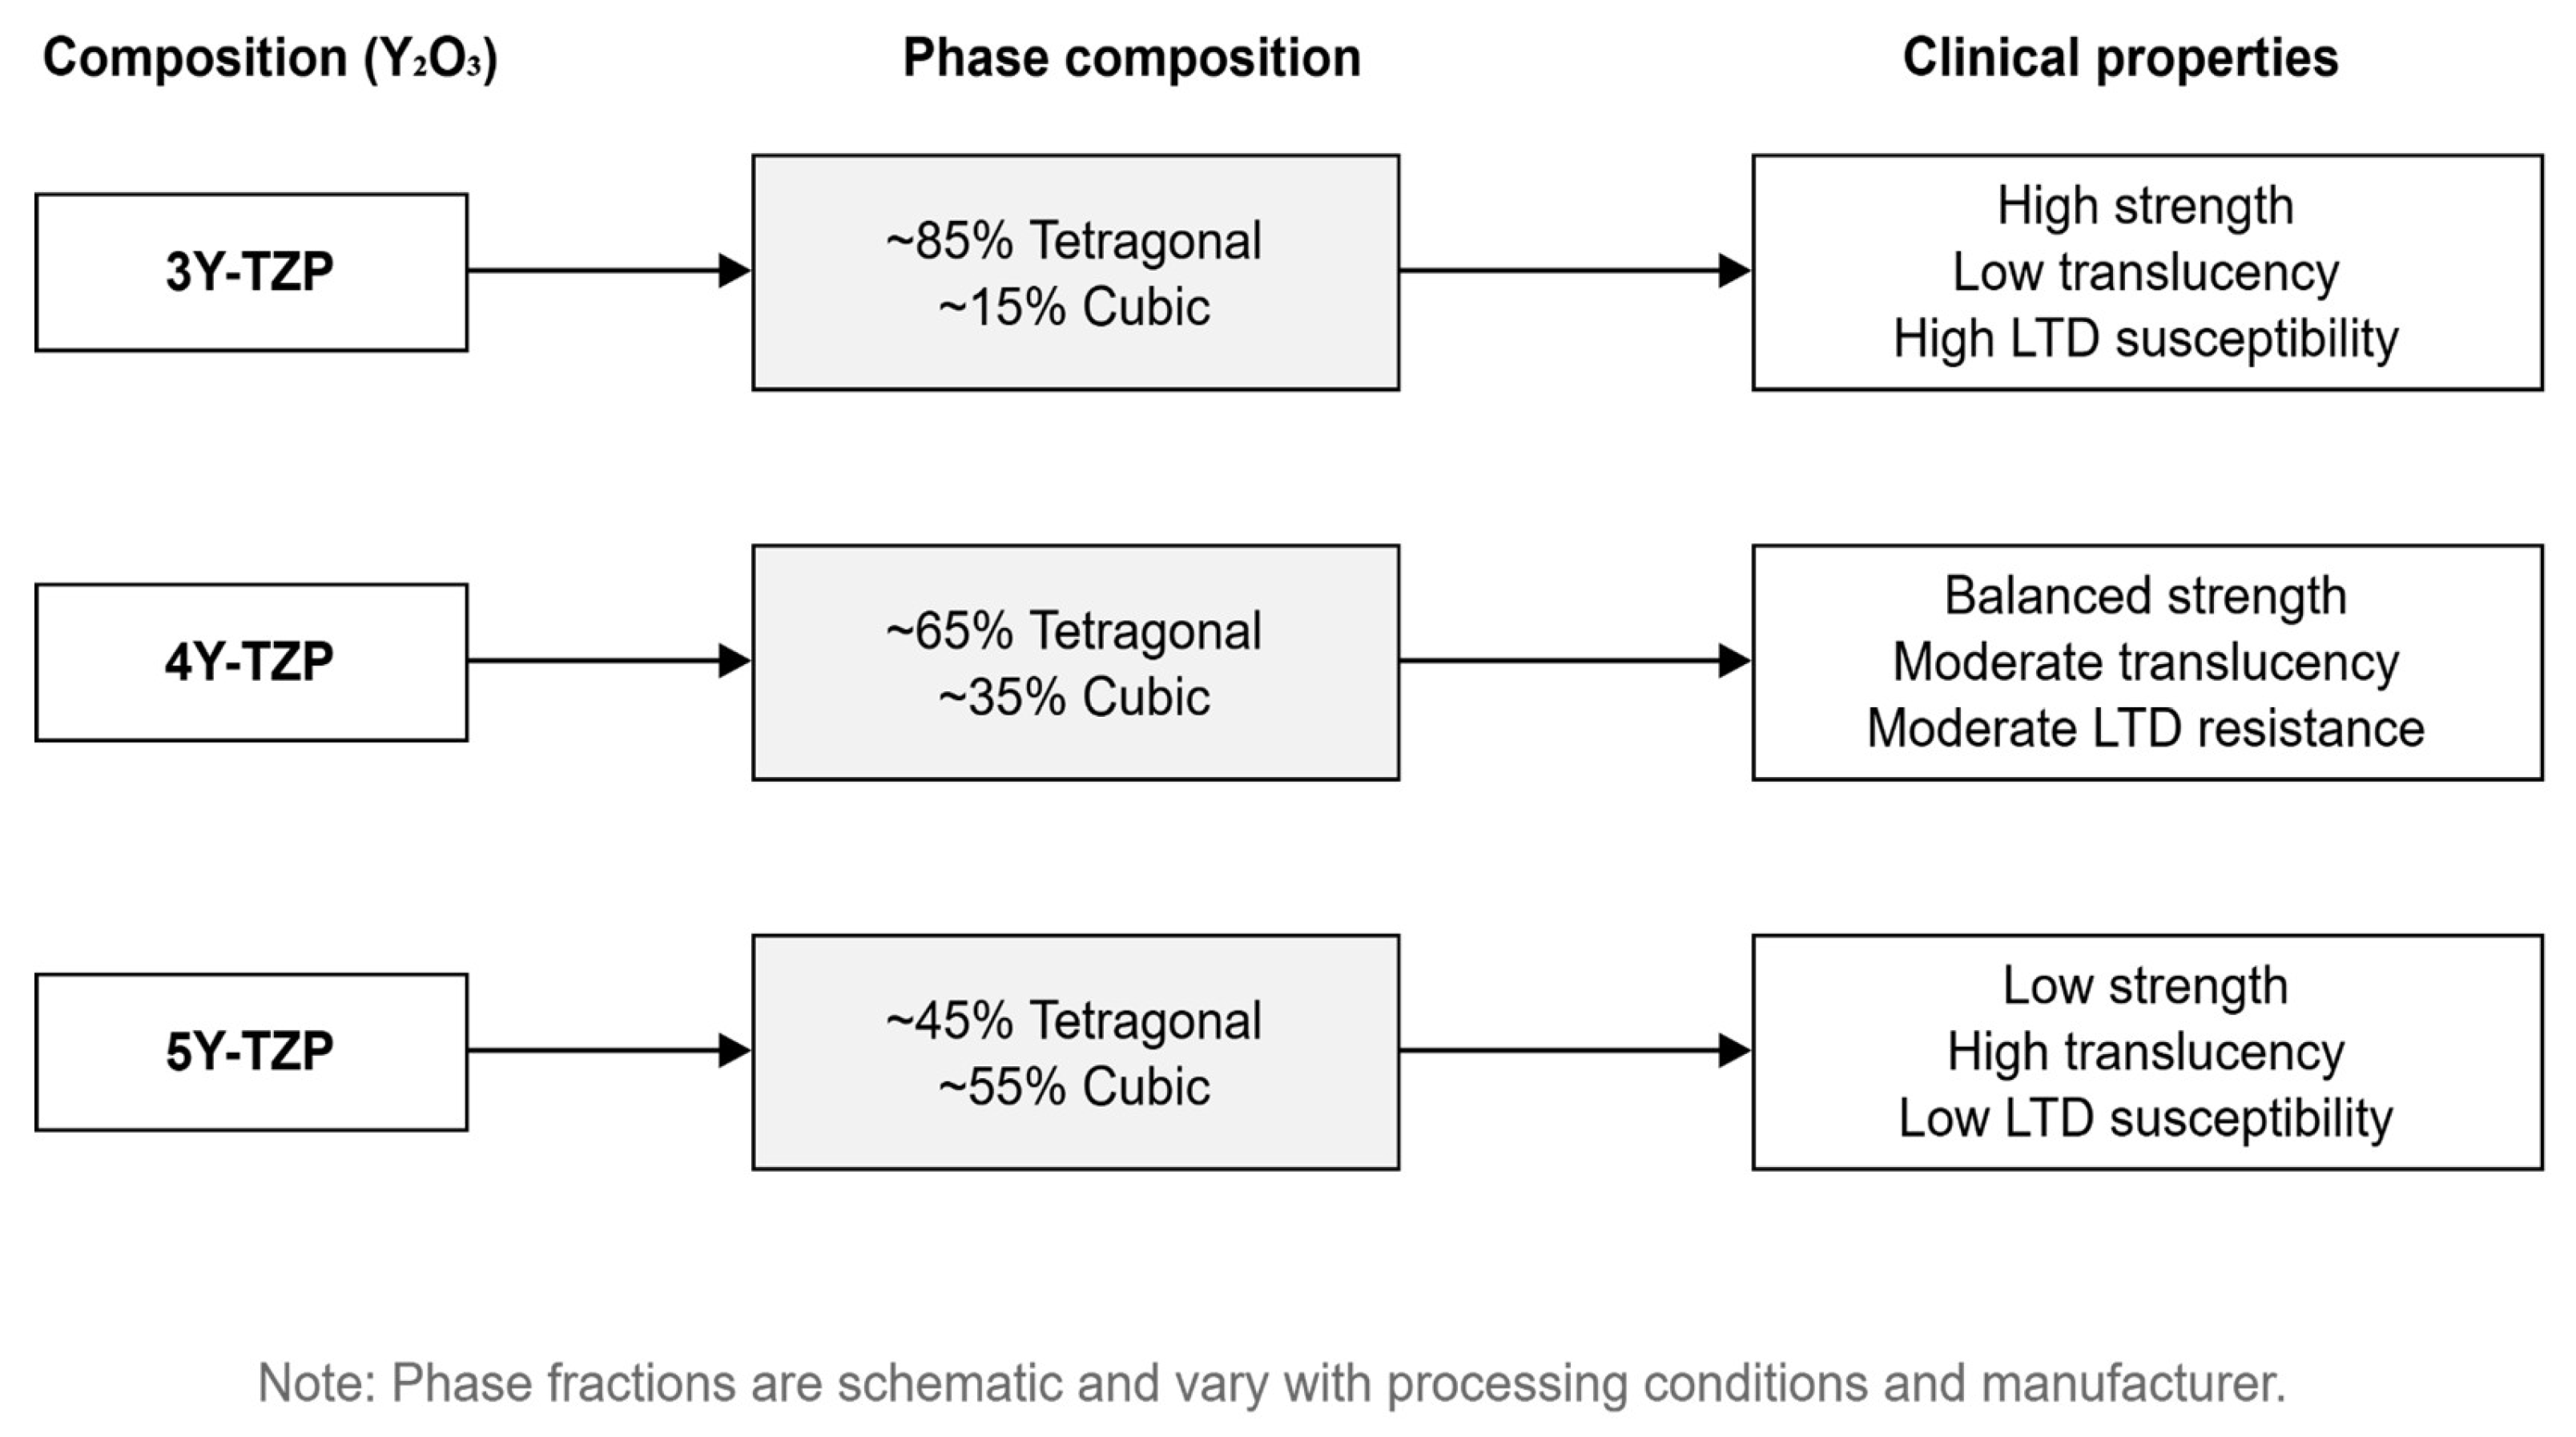
Figure 2.
Classification of dental zirconia along two independent axes: (i) compositional class, defined by yttria content, and (ii) structural design—monolithic (compositionally homogeneous) versus multilayer (vertically graded architecture). Any compositional class may be manufactured in either structural form, so a single generation label alone cannot predict a restoration’s ageing behaviour.
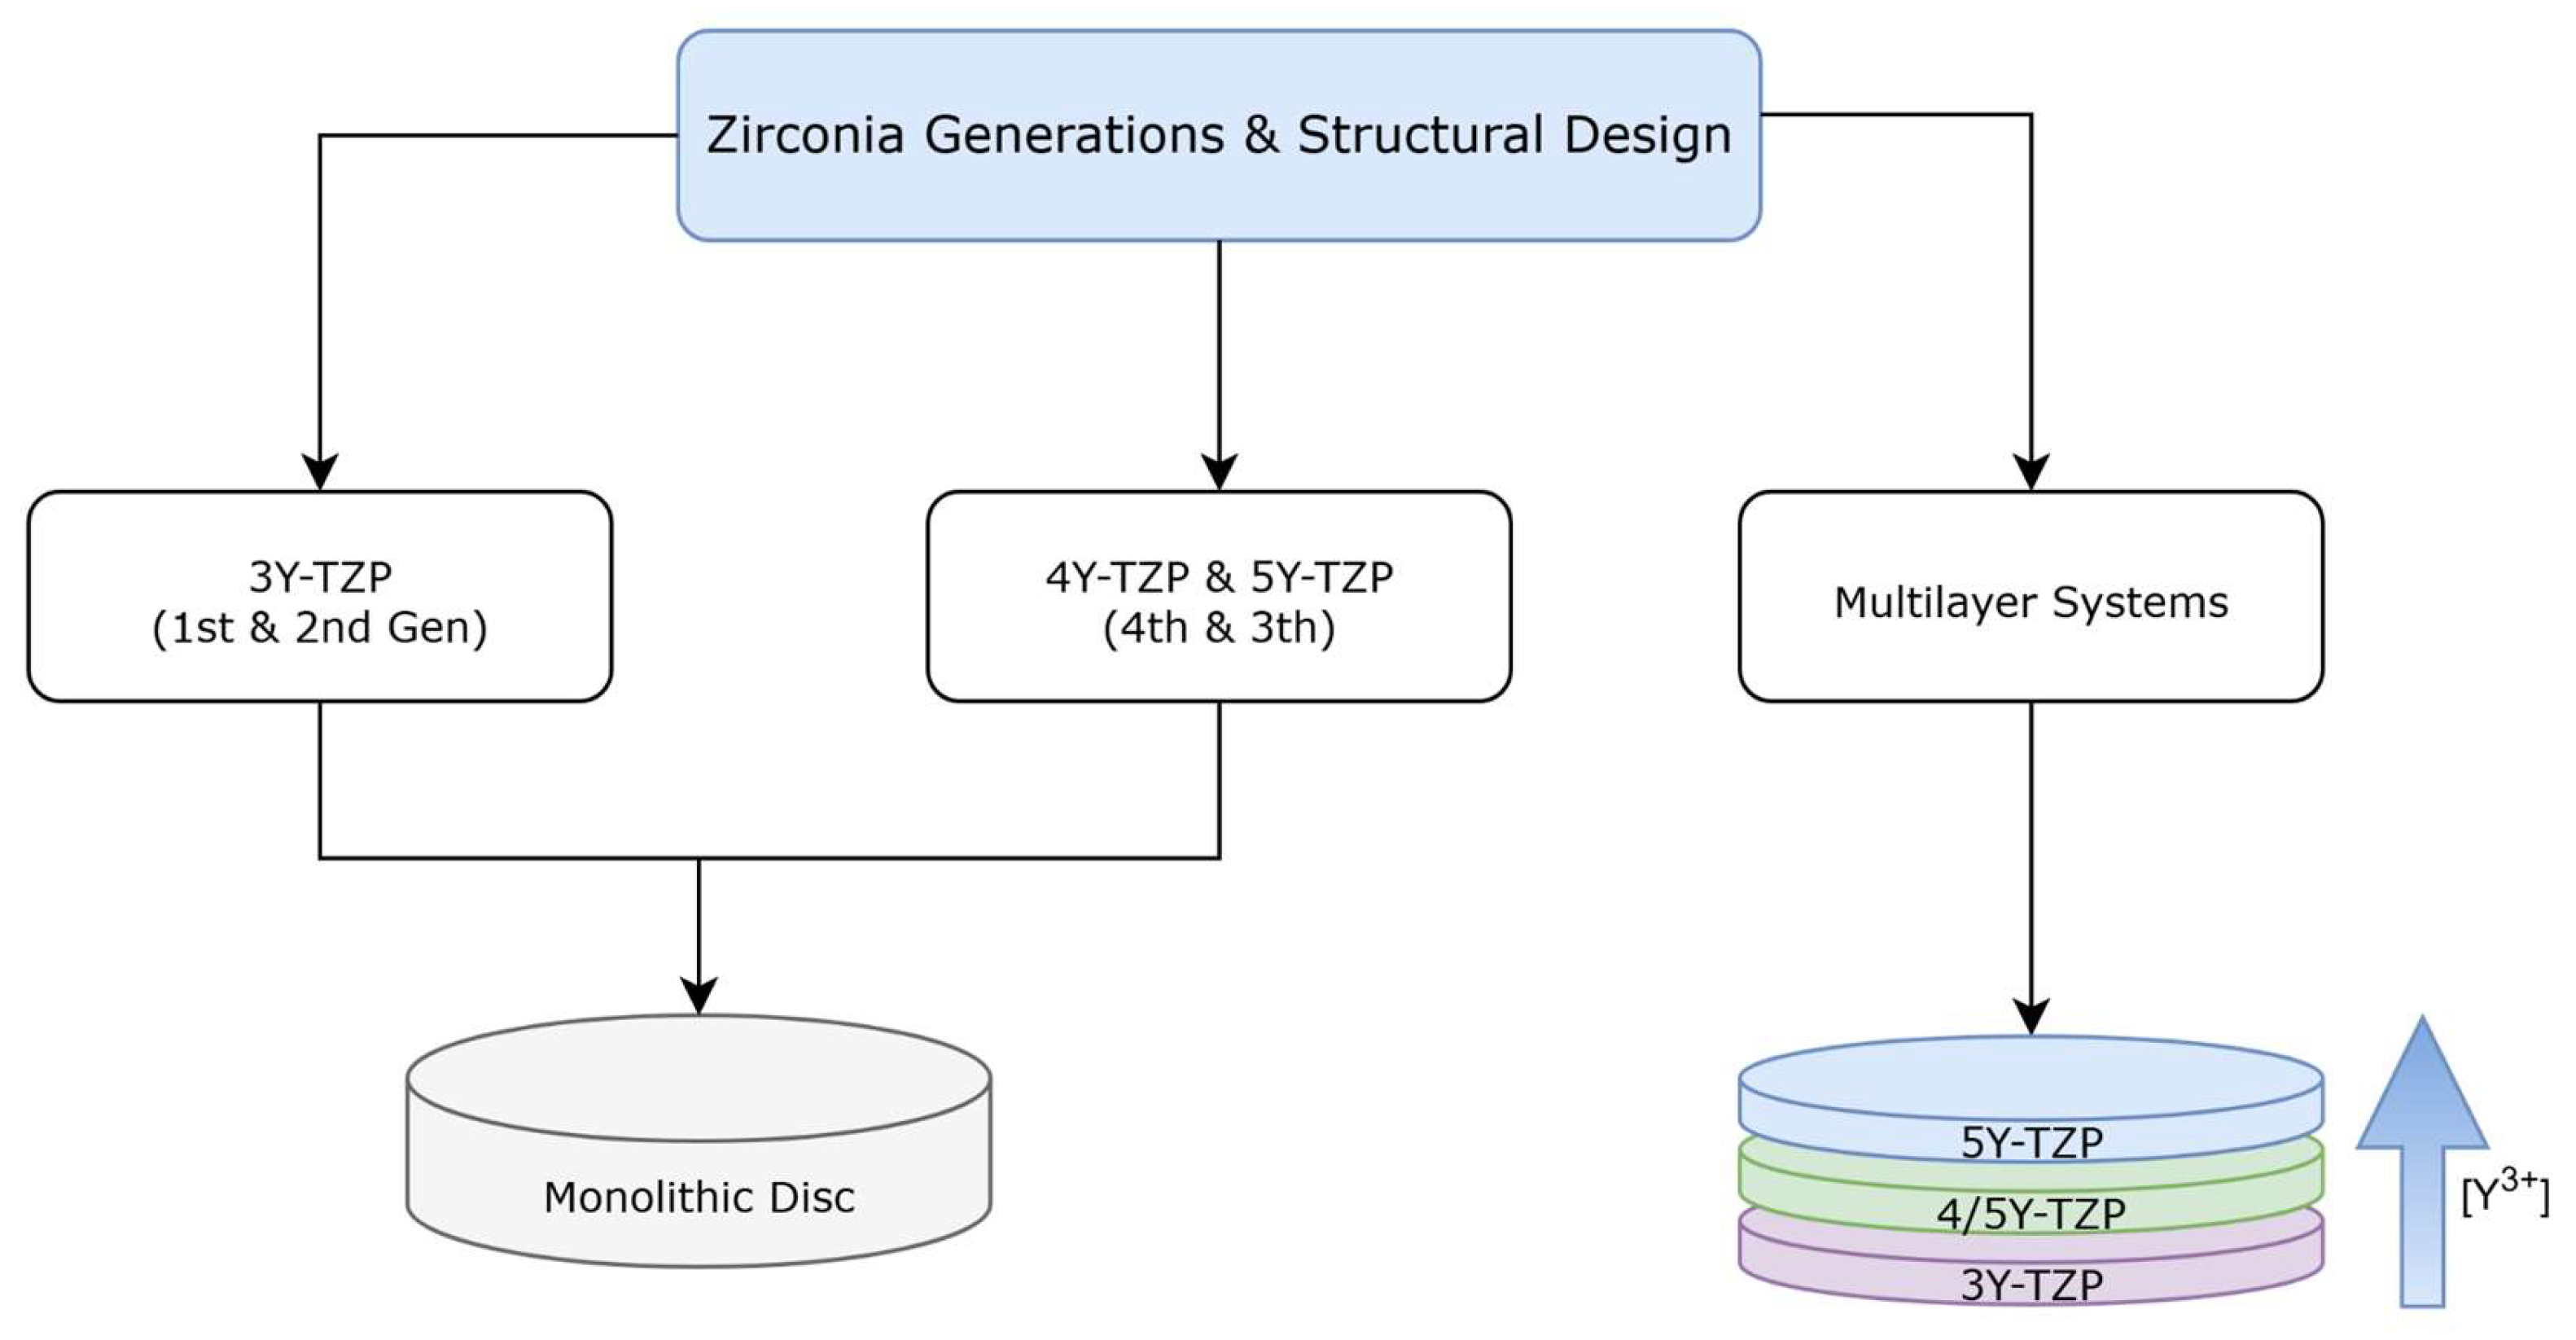
Figure 3.
Schematic overview of the principal artificial ageing methodologies applied to zirconia in fixed prosthodontics. A central zirconia restoration is shown subjected to four primary categories of simulated environmental stress—hydrothermal, thermomechanical, chemical, and optical—each targeting a distinct degradation pathway. The dashed overlay denotes integrated, clinically related combined protocols that reproduce the multifactorial nature of the oral environment by acting on more than one domain simultaneously.
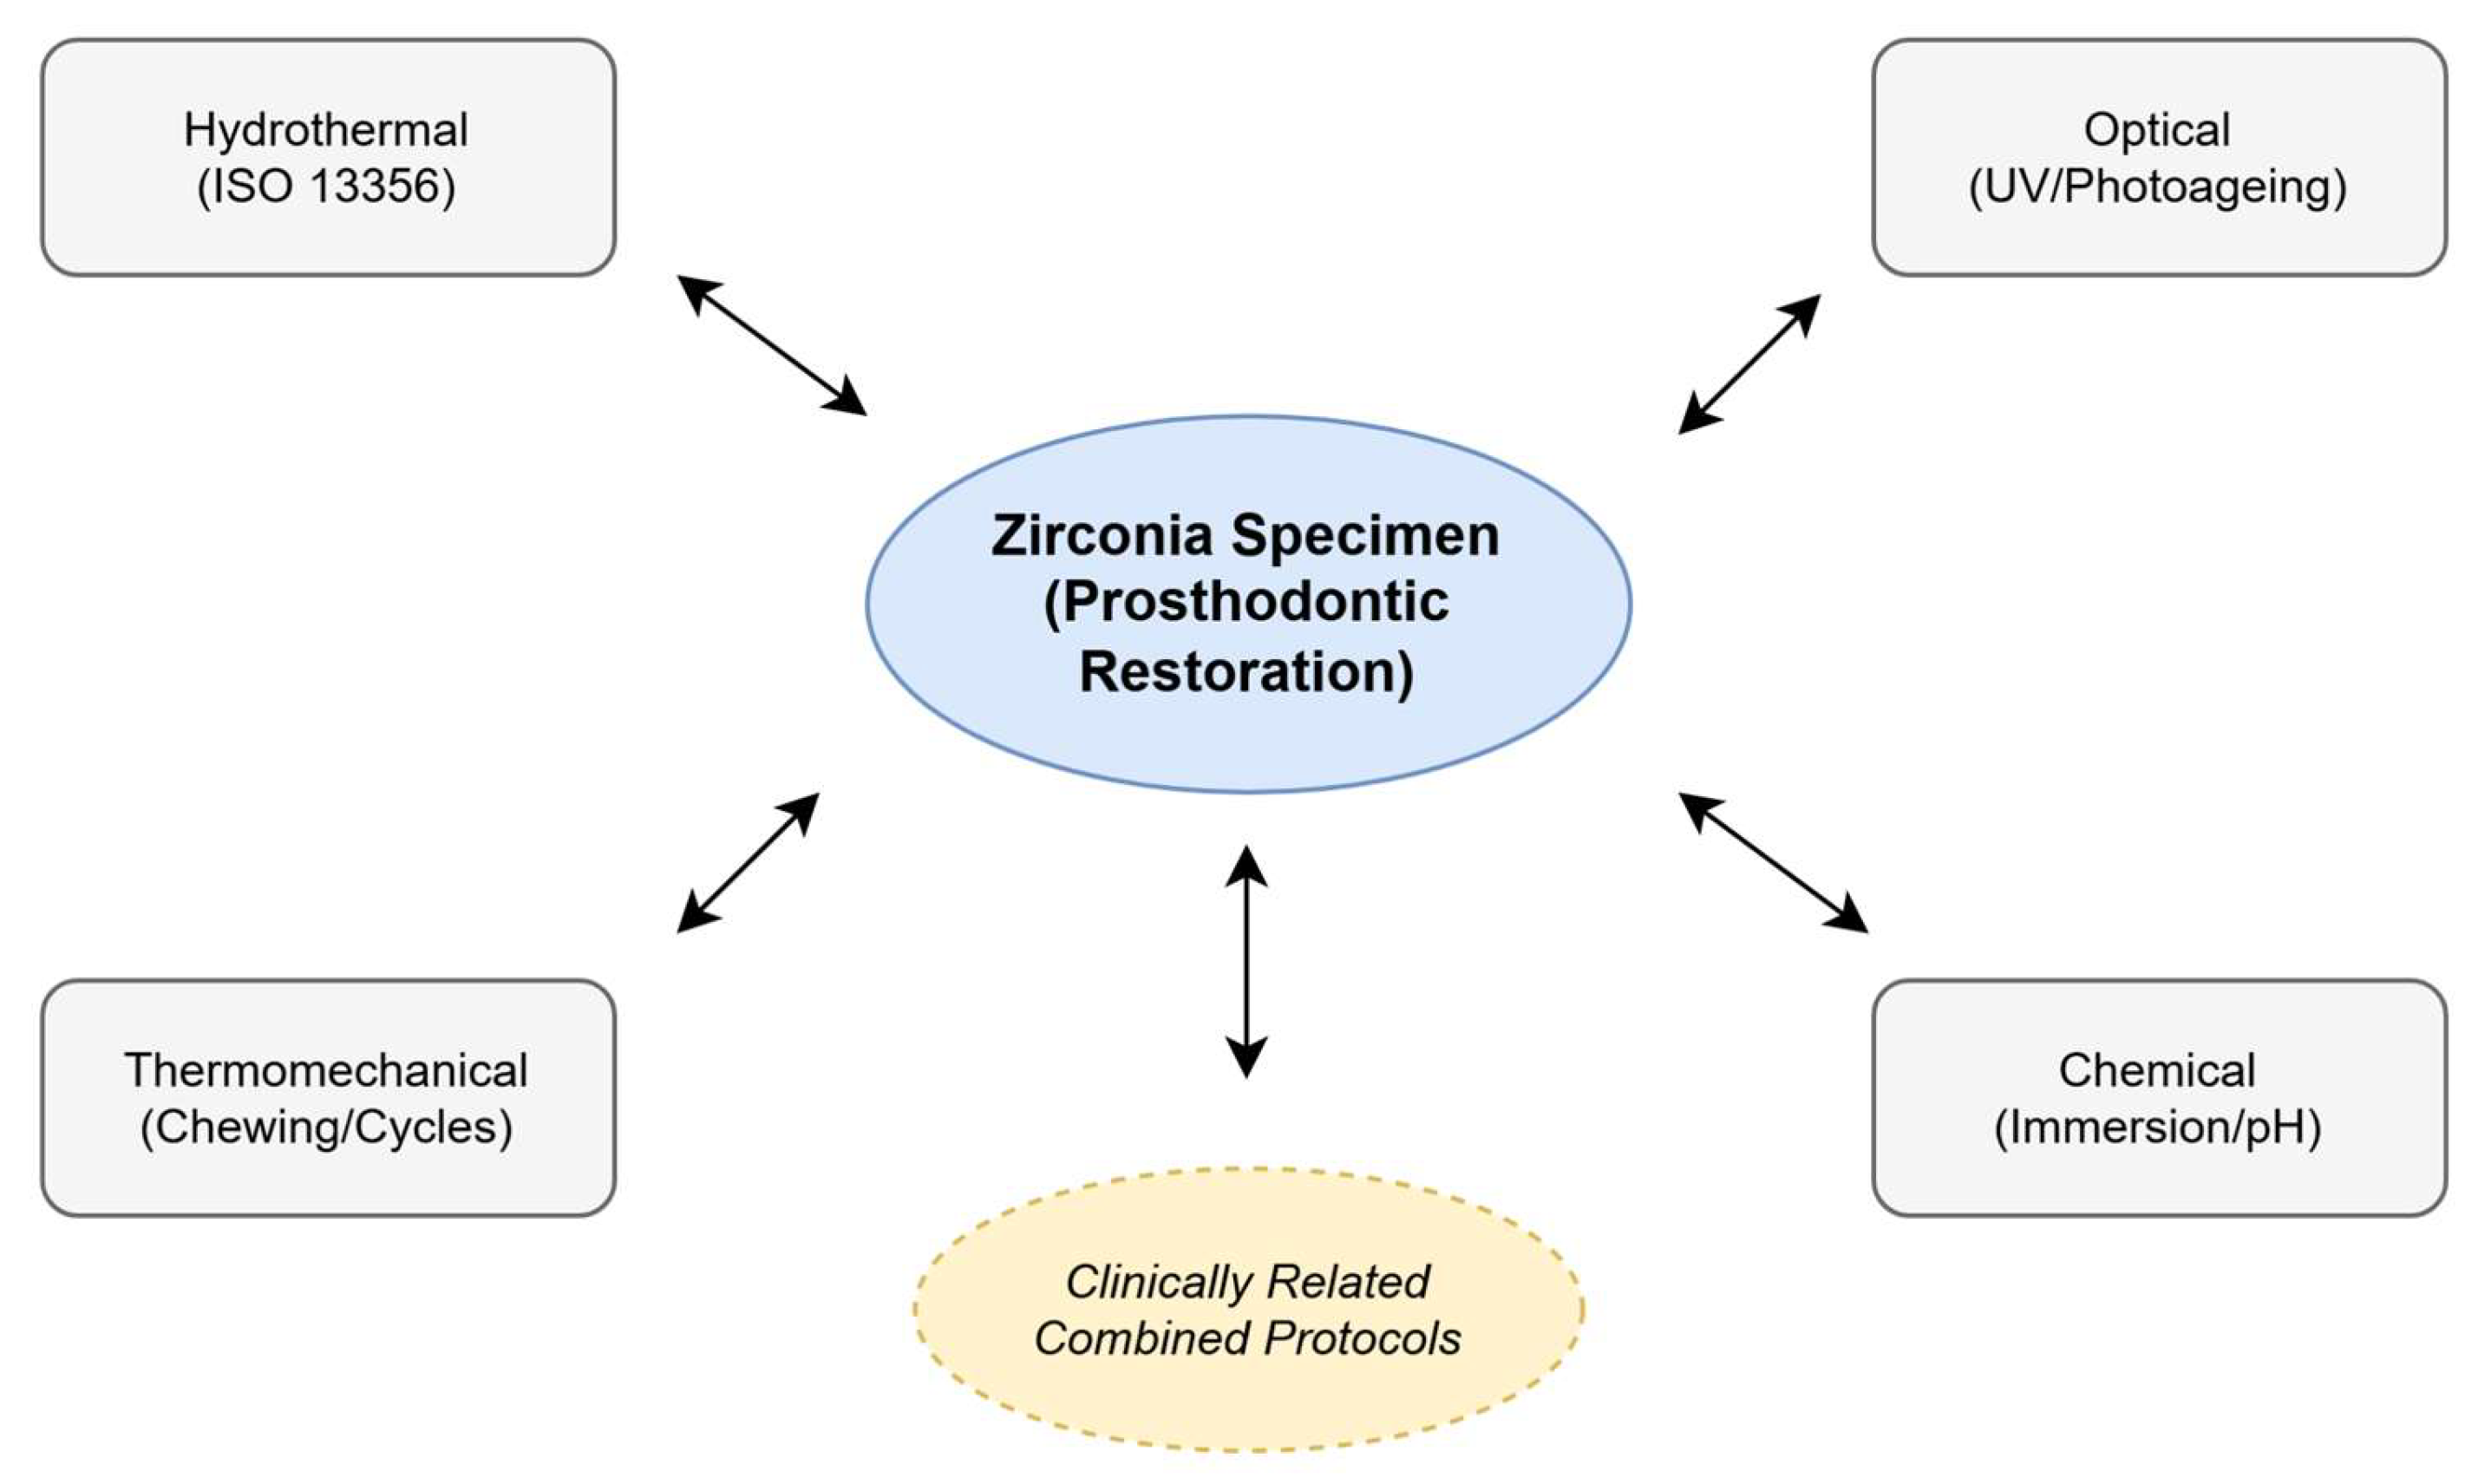
Figure 4.
Bibliometric trends in zirconia ageing research, based on a programmatic analysis of PubMed records (2016–2026). Annual publication counts are tracked across four themes—material generations, artificial ageing, clinical validation, and formal ISO testing standards—illustrating the widening fragmentation gap between rapidly expanding heterogeneous custom-design studies and comparatively static formal-standard investigations.
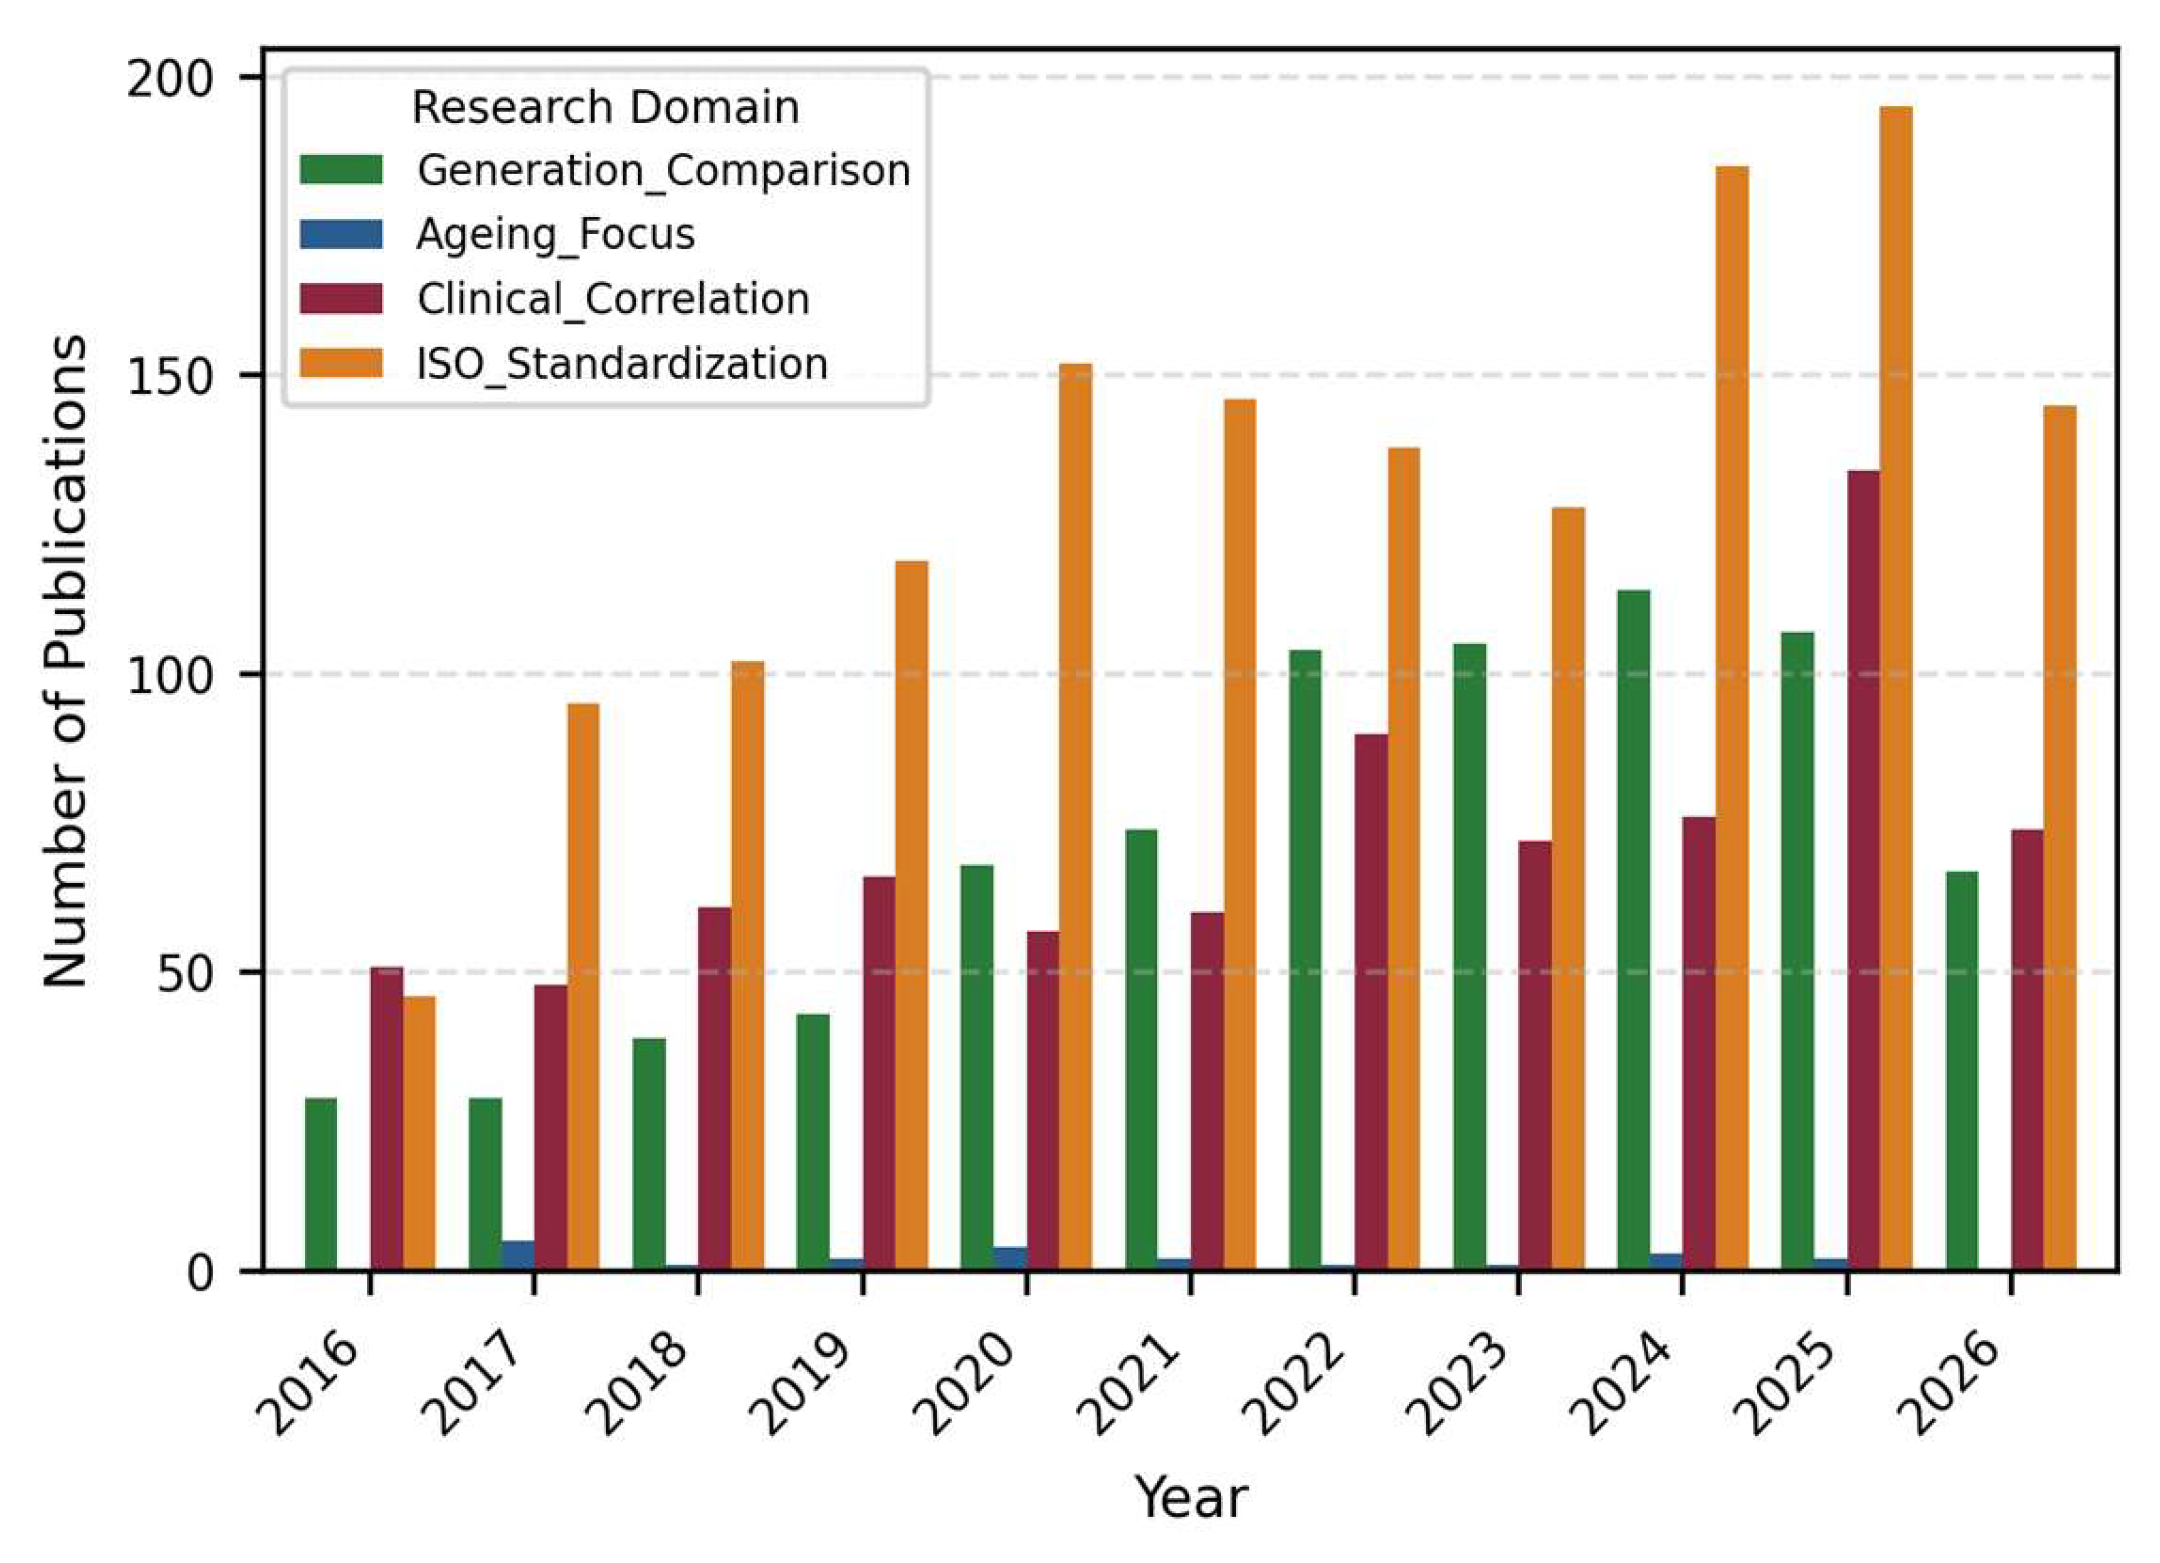
Figure 5.
Layered architecture of zirconia experimental data reporting and analysis. The MIAZE data-reporting layer occupies the foundational level, while independent, interchangeable analytical approaches—kinetic modelling, statistical regression, and machine learning—operate above it as swappable modules, none of which is prescribed or constrained by the reporting standard itself.
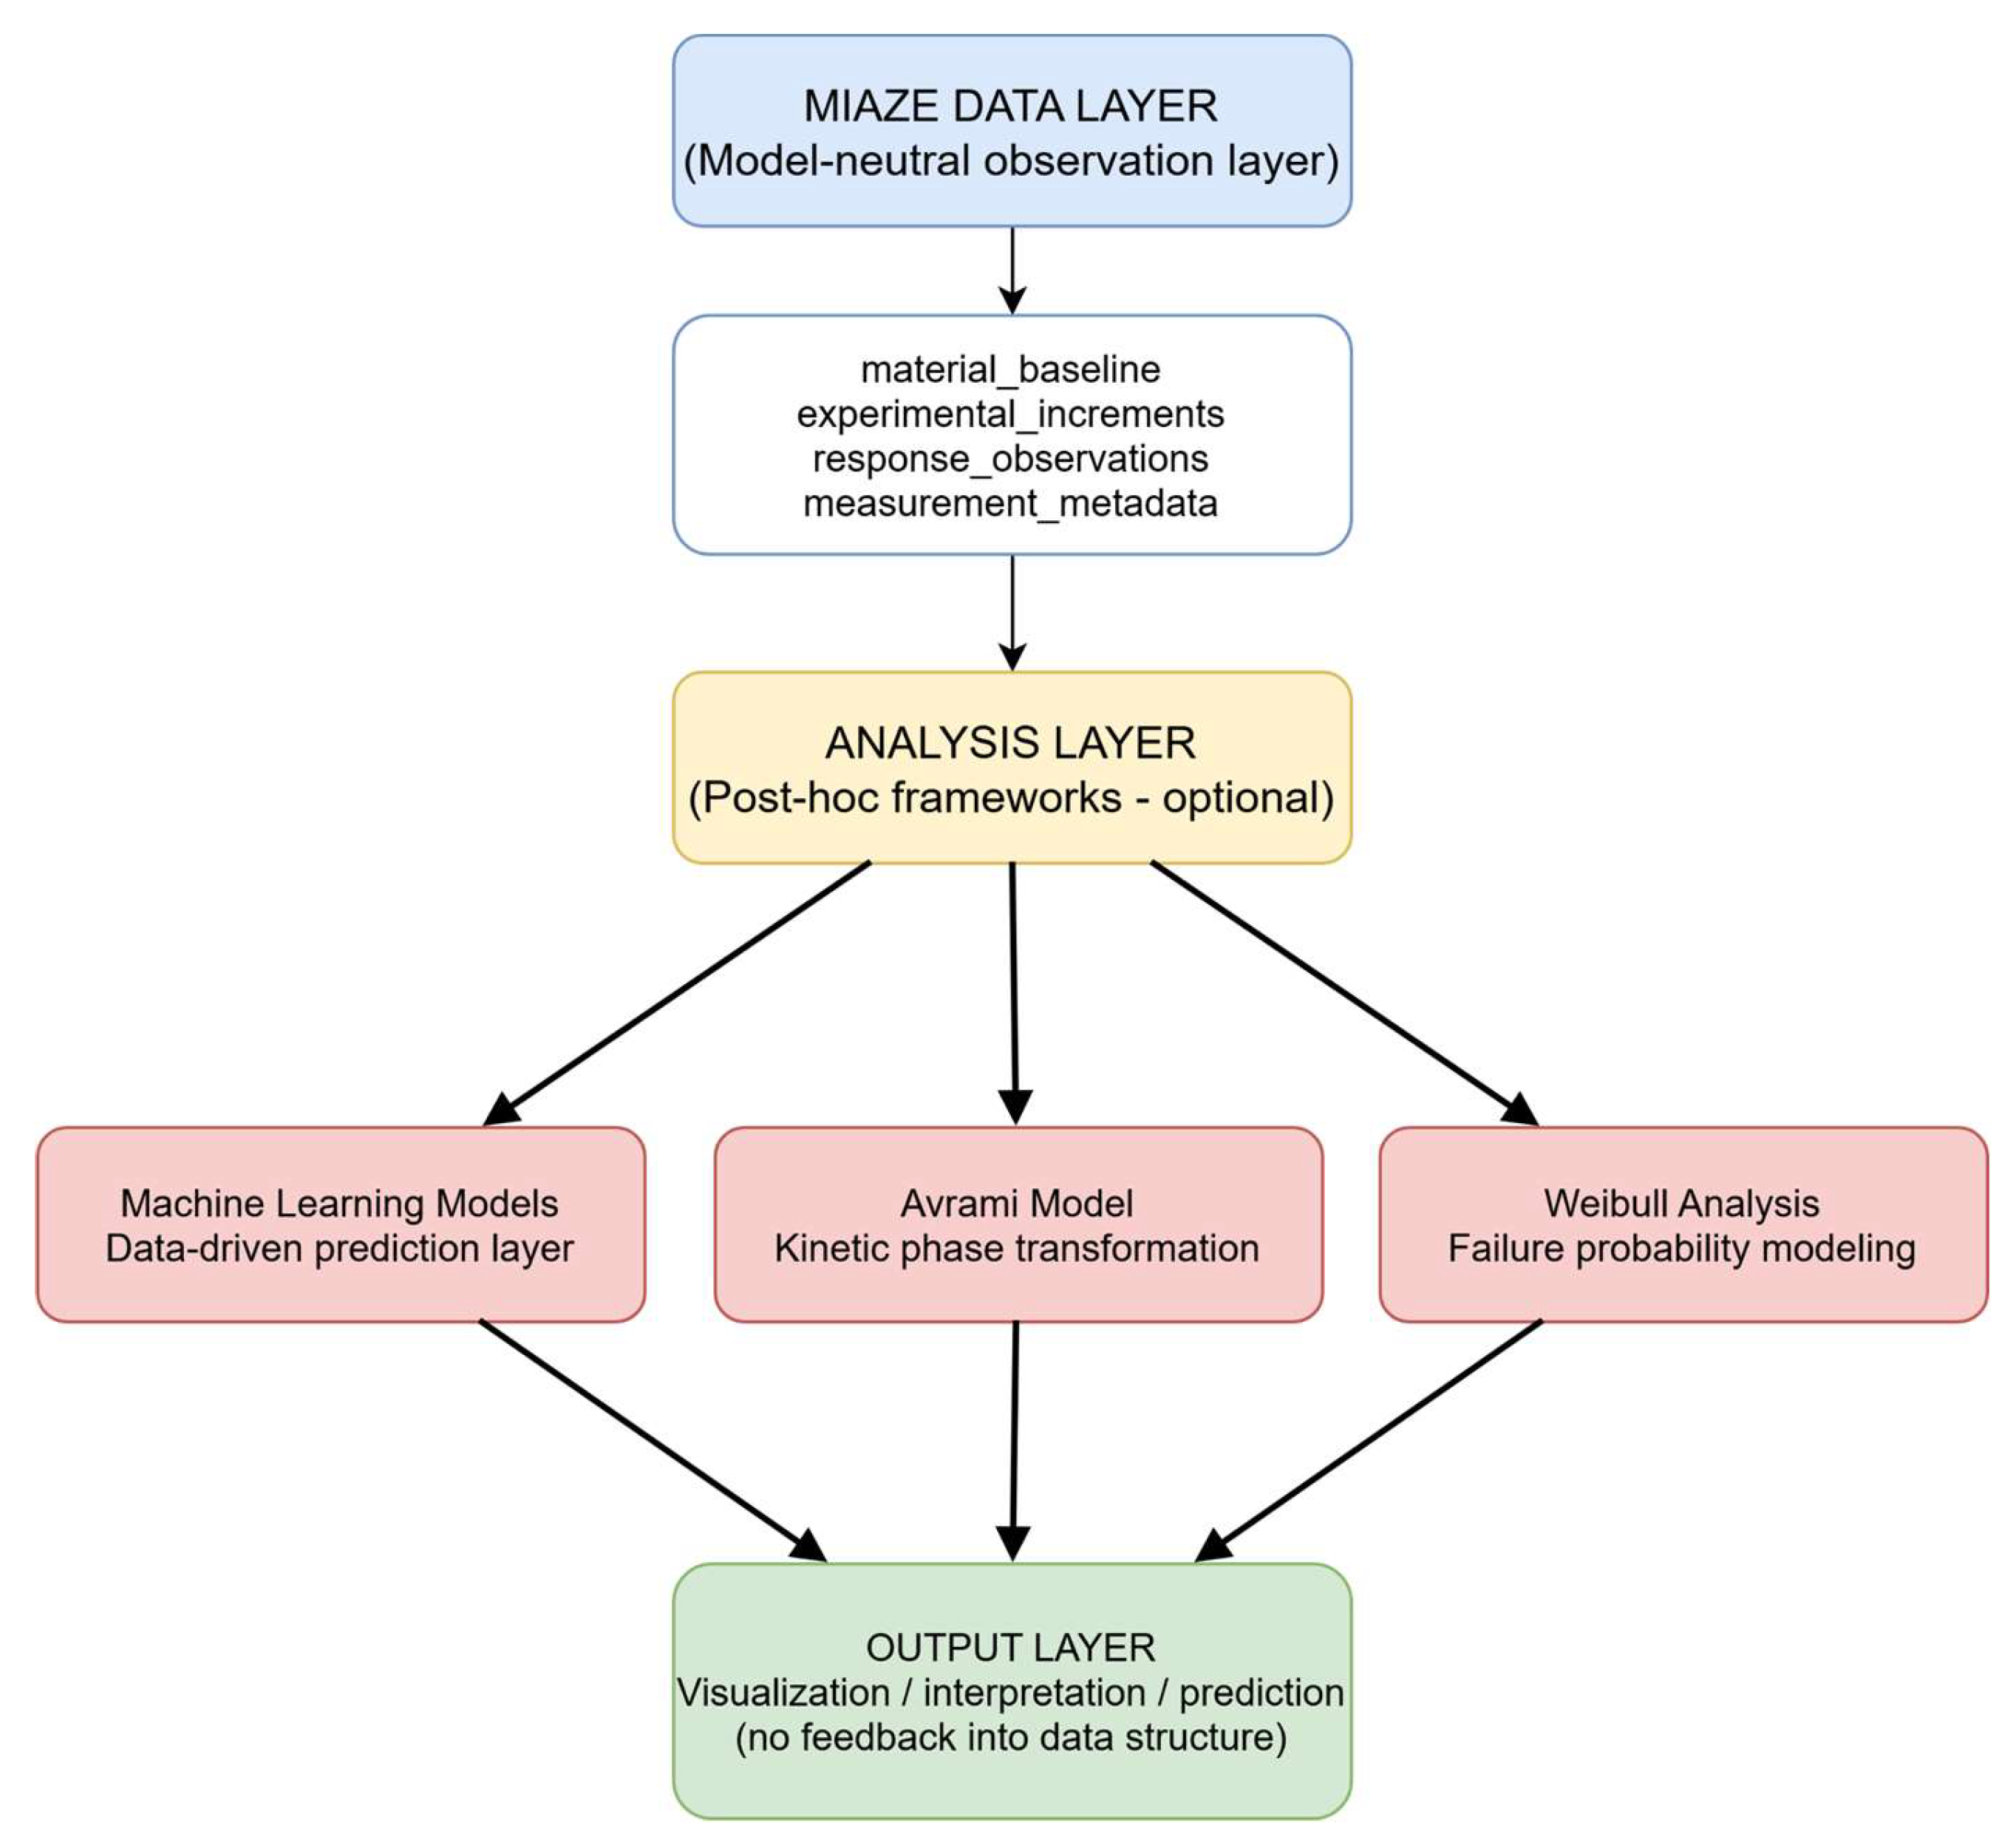
Figure 6.
Patient-centred material-selection scheme relating anatomical position, aesthetic requirement, and functional load-bearing demand. The scheme supports shared clinical decision-making by framing material choice around the fundamental translucency–strength trade-off governed by yttria content.
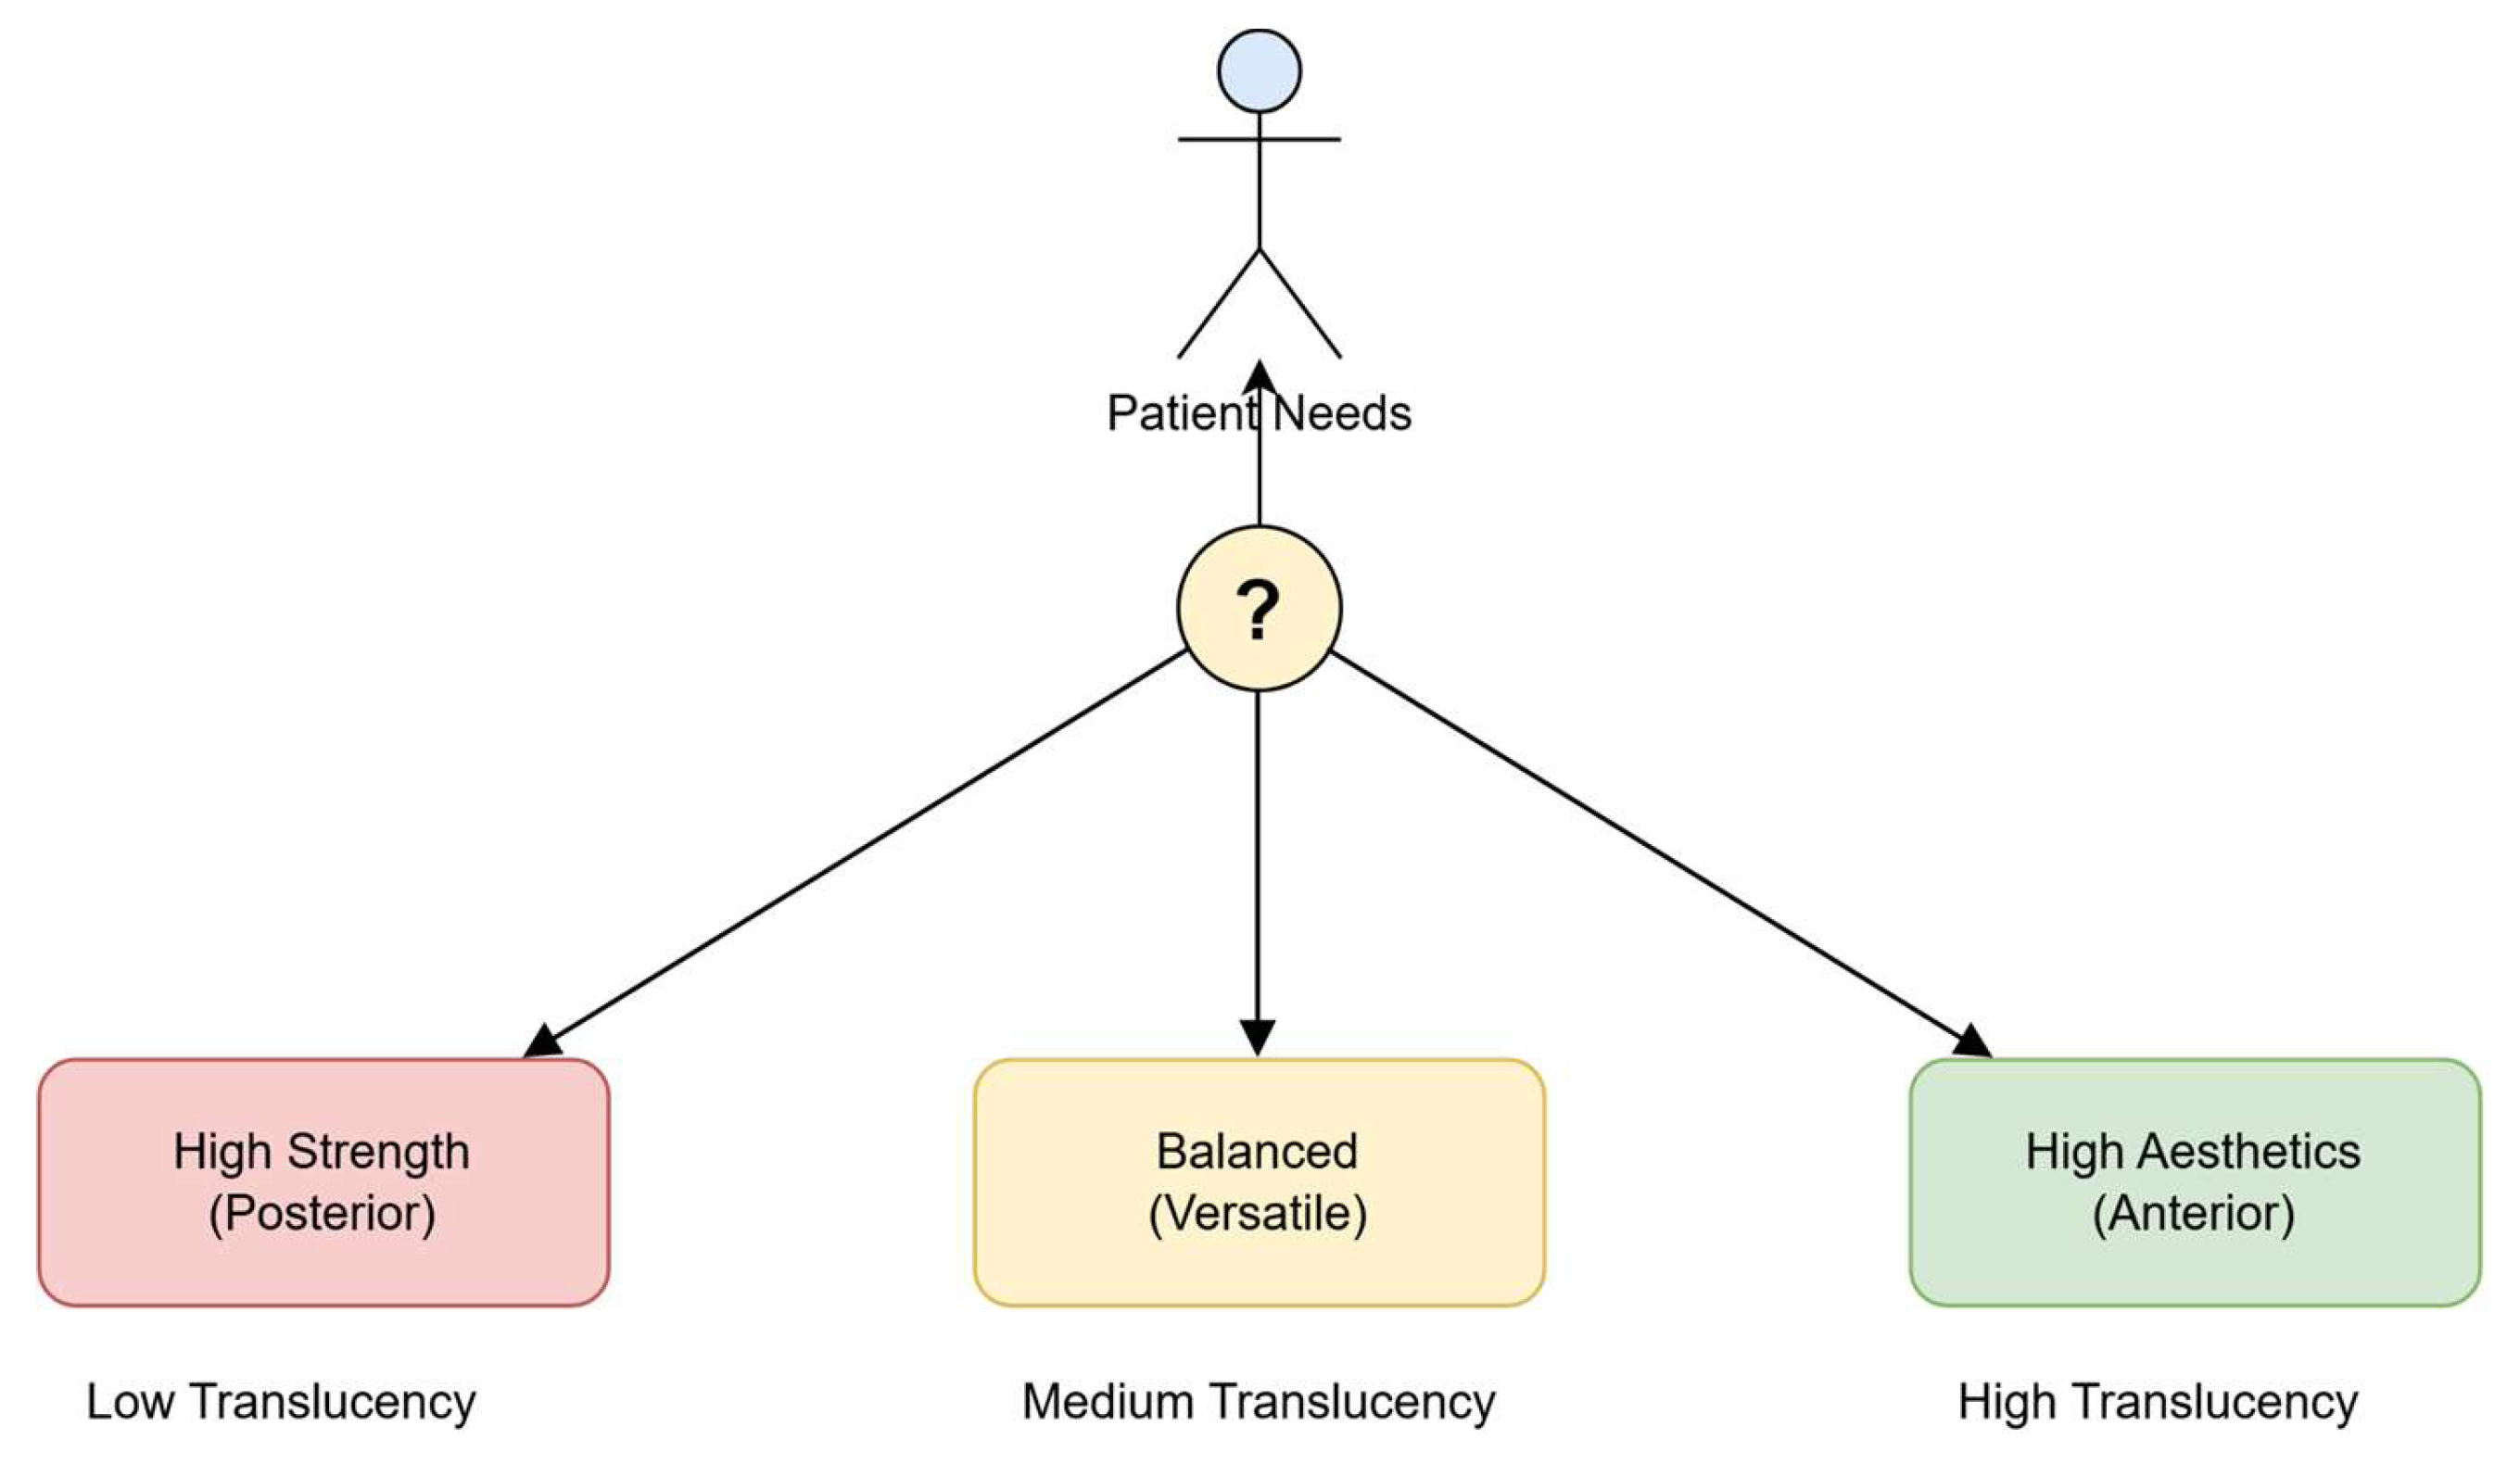
Figure 7.
Clinical decision tree integrating zirconia composition, microstructure, and ageing behaviour into an evidence-based material-selection workflow, aligning material properties with anatomical position, aesthetic demand, and functional load. The reliability of the tree depends on standardised, comparable input data of the kind the MIAZE framework is designed to preserve.
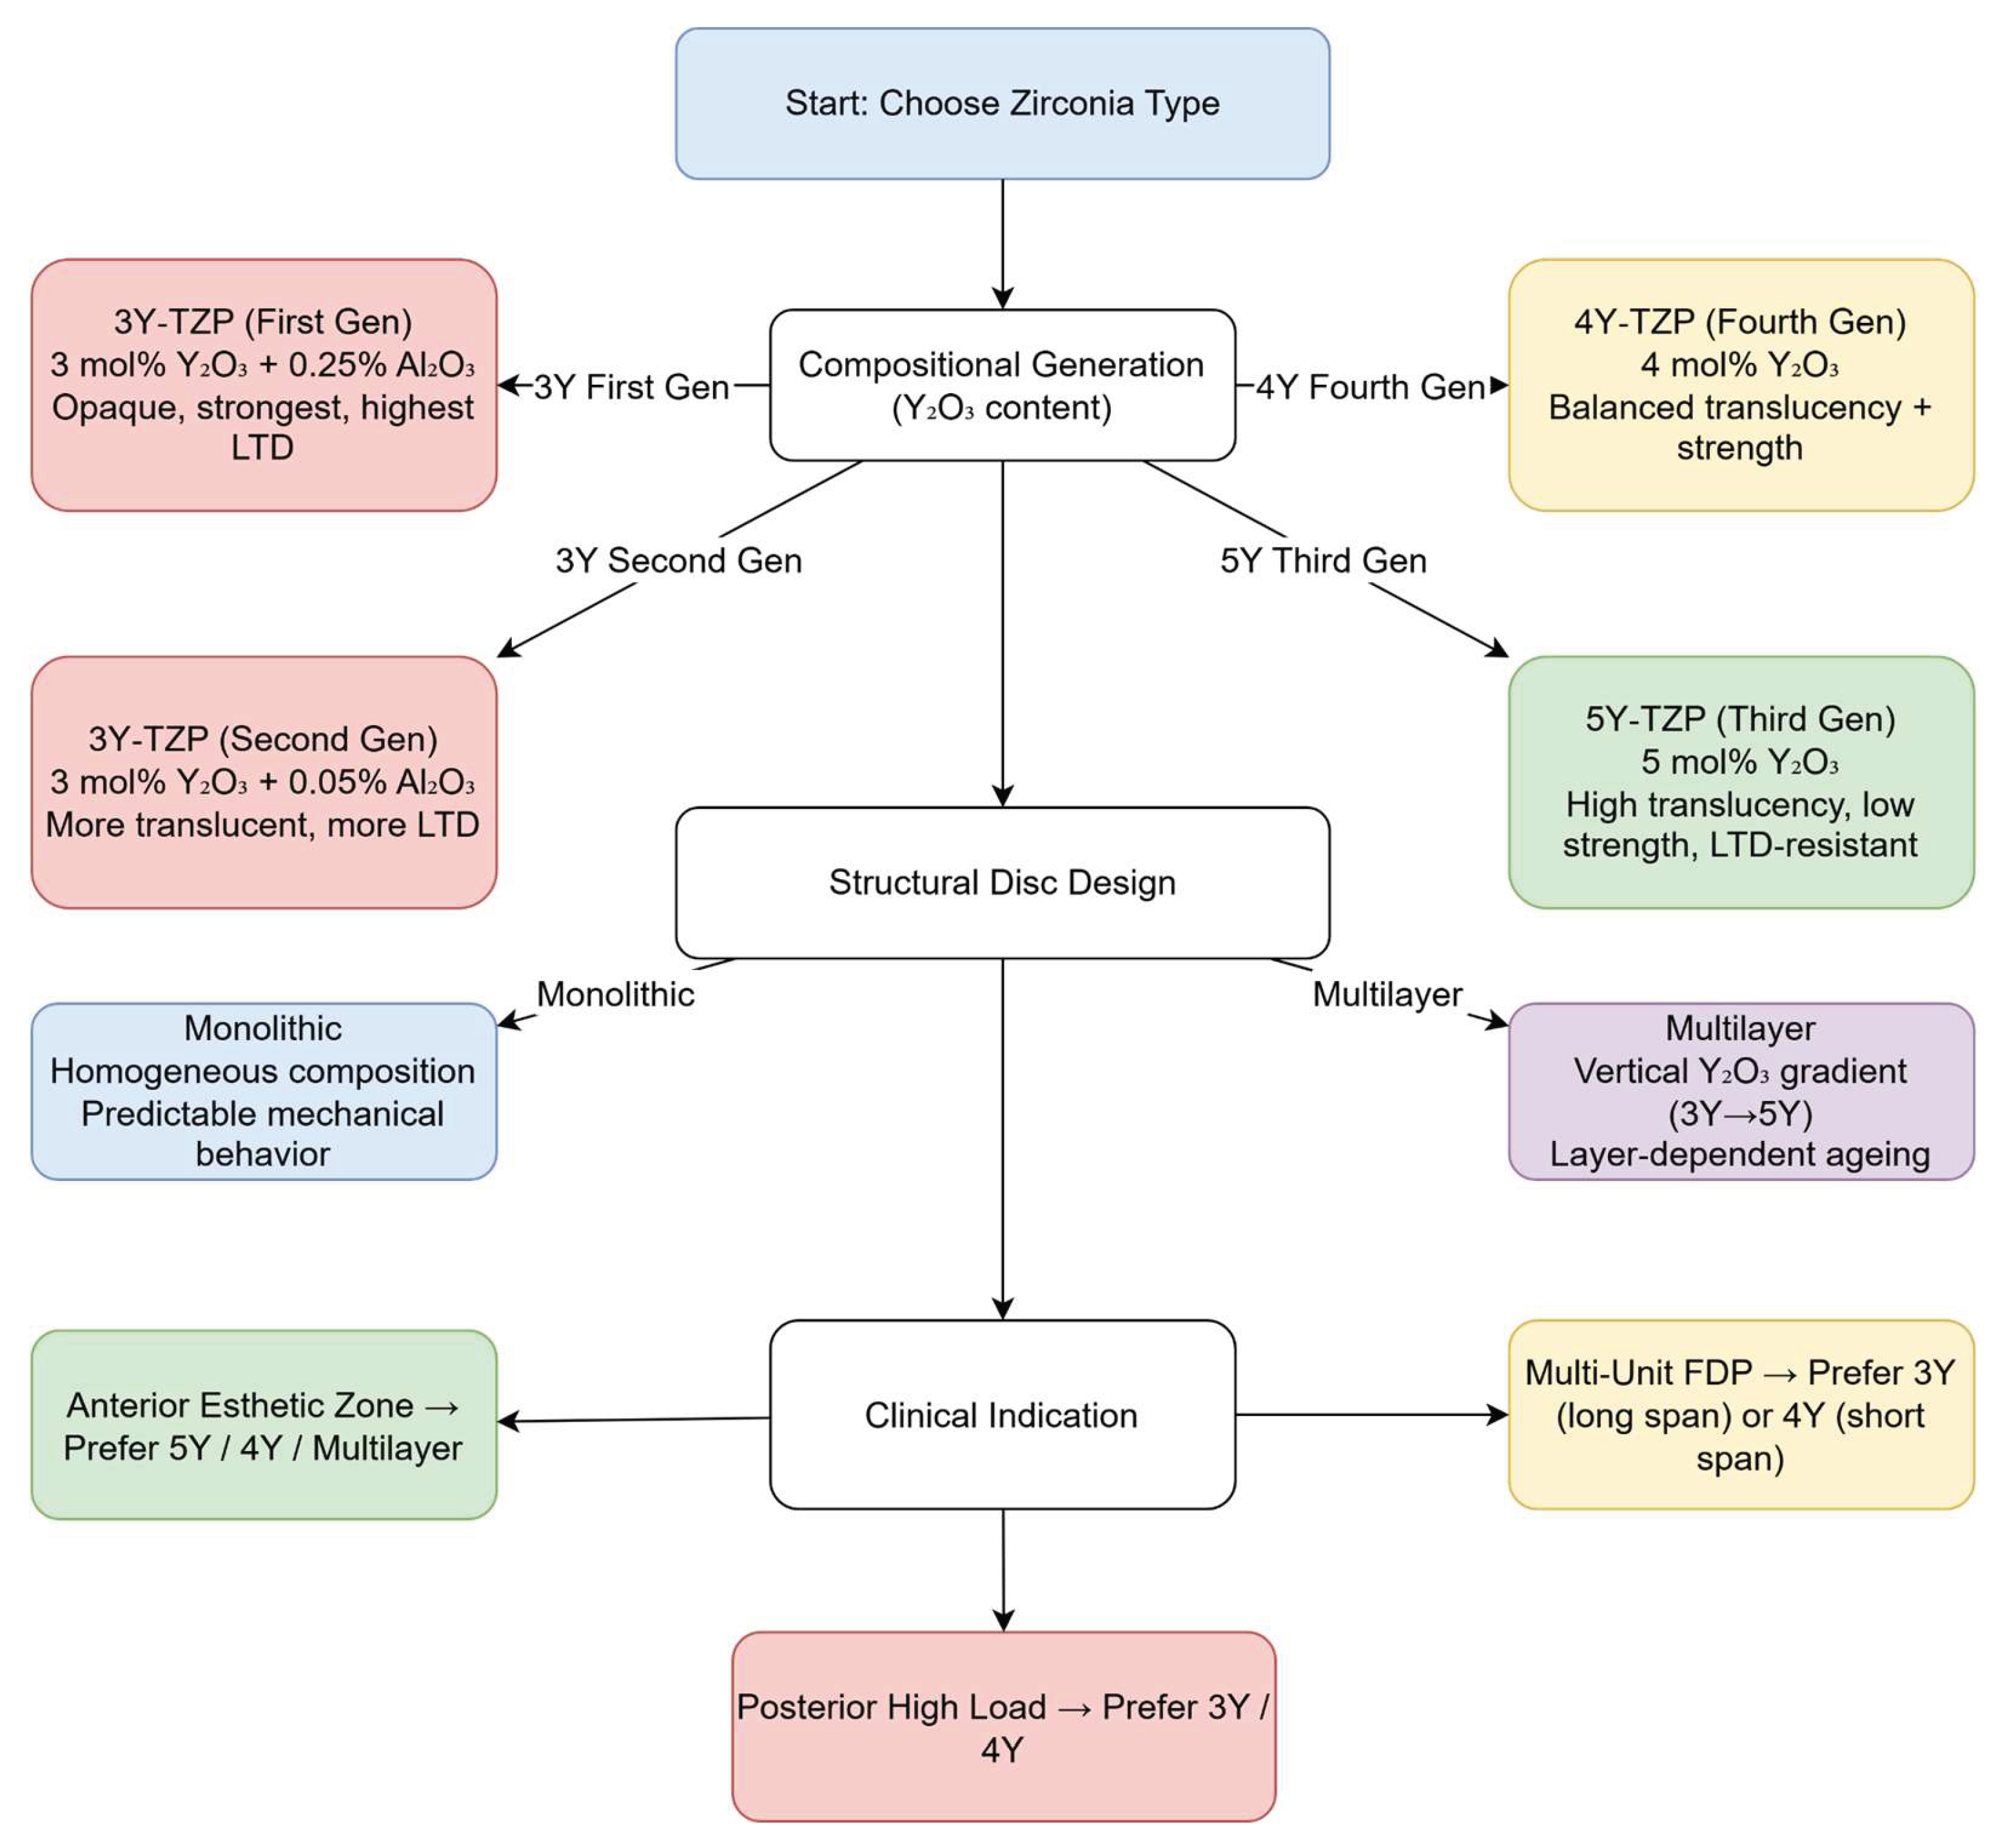

Table 1.
Comparative summary of the principal artificial ageing methodologies applied to zirconia in fixed prosthodontics, giving the mechanism assessed, representative parameter ranges reported in the literature, typical instrumentation and outcome measures, the principal limitations of each approach, and the closest applicable ISO/ADA reference.
| Method | Parameters reported in literature | Equipment | Outcomes assessed | Limitations | ISO/ADA ref. |
|---|---|---|---|---|---|
| Hydrothermal (autoclave) | 110–140 °C; 0.2–2 bar; 5–64 h. Most common: 134 °C, 2 bar, 5 h (ISO). Research extends to 54 h. | Autoclave (steam-pressure vessel) | Phase transformation (XRD), flexural strength, surface roughness, SEM, microhardness | Highly accelerated; time–temperature extrapolation debated; overestimates LTD in high-yttria zirconia | ISO 13356 |
| Thermocycling | 5–55 °C (most common); 5–60 °C or 5–75 °C for greater stress. Cycles: 600–50,000 (10,000 ≈ 1 year). Dwell: 20–30 s. | Thermocycler/water-bath device | Bond strength, microhardness, colour (ΔE), marginal integrity, phase content | Wide variability in cycle number, dwell time and temperature range; poor inter-study comparability | ISO 6872; ADA No. 27 |
| Chewing/masticatory simulation | 1.2 × 10⁶ cycles (≈5 years); 50–200 N; 1.0–1.6 Hz; 37 °C water bath. Often combined with thermocycling. | Chewing simulator (Willytec, Korrvu, etc.) | Fracture load, survival, surface wear, phase transformation, fatigue degradation | Variable loads and cycles; no single accepted protocol; expensive equipment required | ISO 14801 (partial) |
| Chemical immersion | 4% acetic acid at 60–80 °C; HCl pH 1.2; artificial saliva at 37 °C; NaOH; varies widely. | Temperature-controlled bath/oven | Phase transformation, elemental release (ICP), surface roughness, colour stability | Poorly standardised; acid kinetics differ from hydrothermal ageing; limited clinical correlation | ISO 6872 |
| UV/photoageing | 340 nm, 0.55 W/m2; 300–1500 h (Weather-O-meter or UV chamber). Also 365 nm. | UV ageing chamber, Weather-O-meter | Colour stability (CIE ΔE, ΔE00), surface roughness, translucency parameter, microhardness | Primarily relevant for extrinsic colouring; zirconia crystalline structure is UV-stable; low structural relevance | ASTM G154 |
| Clinically related/combined | Chewing simulation (1.2 × 10⁶ cycles) + thermocycling (5,000–50,000 cycles) + chemical immersion (HCl, pH 1.2, 15 h). Sequence varies. | Multiple devices (simulator + thermocycler + bath) | Fracture resistance, optical changes, translucency, colour, surface condition | No protocol consensus; heterogeneous combinations; high resource demand; difficult to isolate variable effects | None defined |
Table 2.
Illustrative, non-exhaustive post-hoc analytical representations, organised as a decision matrix linking a research objective to a material system, an experimental stressor, and an example (non-required) analytical interpretation. The matrix presupposes laboratory data captured at MIAZE-compliant resolution.
| Research objective | Material system | Experimental stressor | Example analytical interpretation (non-required) |
|---|---|---|---|
| Material stability comparison | 3Y, 4Y, 5Y (monolithic zirconia) | Autoclave ageing time (hydrothermal exposure) | Phase-transformation kinetic descriptor (example kinetic descriptor) |
| Fatigue resistance mapping | Multilayer zirconia systems | Mechanical loading (cycles/force amplitude) | Mechanical degradation rate (example degradation metric) |
| Chemical/corrosion response | 3Y, 4Y, 5Y (flat disc specimens) | pH exposure/chemical immersion duration | Surface degradation index (example response slope, model-dependent) |
| Multi-variable optimisation | All zirconia variants | Combined stressors (temperature, pH, load, time) | Multidimensional stability vector (feature-space representation) |
Table 3.
Recurring methodological limitations in the zirconia ageing literature mapped onto representative post-hoc analytical approaches, with the rationale linking each approach to the specific MIAZE reporting element that makes it applicable. The mapping is interpretive rather than prescriptive.
Table 3.
Recurring methodological limitations in the zirconia ageing literature mapped onto representative post-hoc analytical approaches, with the rationale linking each approach to the specific MIAZE reporting element that makes it applicable. The mapping is interpretive rather than prescriptive.
| Current narrative limitation | Example analytical approaches | Rationale |
|---|---|---|
| Speculative clinical time extrapolations | Kinetic modelling, statistical regression | Relies on raw experimental increments and response observations rather than assumed clinical-year equivalencies, so time-extrapolation claims can be recalculated as models improve. |
| Equipment-specific variability | Reference normalisation, statistical calibration | Uses measurement metadata (instrumentation, calibration, uncertainty) to correct for inter-laboratory differences instead of treating results as directly comparable. |
| Heterogeneous specimen geometries | Finite element-informed correction, subgroup analysis | Captures specimen design within material baseline, allowing geometry-driven effects to be isolated rather than folded into the reported response. |
| Qualitative or pass/fail reporting | Continuous response modelling, probabilistic methods | Requires response observations to be reported as measured values rather than binary outcomes, preserving the granularity needed for quantitative modelling. |
Table 4.
The MIAZE reporting schema. The four minimum reporting elements are listed with their required JSON keys, required observational fields, and the rationale by which each element preserves observation primacy at the data-infrastructure layer.
Table 4.
The MIAZE reporting schema. The four minimum reporting elements are listed with their required JSON keys, required observational fields, and the rationale by which each element preserves observation primacy at the data-infrastructure layer.
| Data category | Required JSON key | Required observational fields | Rationale for observation primacy |
|---|---|---|---|
| Material baseline | material_baseline | Manufacturer, batch identifier, yttria content (mol%), specimen design (monolithic/multilayer), and initial phase composition | Establishes the immutable provenance and composition of the specimen before experimental stress |
| Experimental increments | experimental_increments | Stress type (e.g., hydrothermal, mechanical), units (e.g., hours, cycles), and independent-variable values | Documents the raw stress conditions applied, without analytical transformation or temporal extrapolation |
| Response observations | response_observations | Measured response type (e.g., monoclinic %), units, and raw observational values | Records direct experimental outcomes; excludes derived kinetic slopes, regression coefficients, or fitted parameters |
| Measurement metadata | measurement_metadata | Instrumentation, acquisition parameters, spatial/temporal resolution, and associated uncertainty margin | Ensures technical reproducibility by documenting the precision and conditions of data acquisition |
Table 5.
Worked example of structured comparison across analytical approaches, showing how a shared MIAZE dataset structure (specimen identifier, stress increments x, observed response y) supports interchangeable, method-dependent analytical outputs and comparative interpretation without altering the underlying data.
| Specimen identifier | Stress increments (x) | Observed response (y) | Example analytical output | Comparative interpretation |
|---|---|---|---|---|
| 3Y-TZP reference | x1, x2, x3 | y1, y2, y3 | Model-derived kinetic or statistical descriptor | Baseline reference within selected analytical context |
| Target material A |
x1, x2, x3 | y1, y2, y3 | Model-derived descriptor (method-dependent) | Interpretation depends on selected analytical approach |
| Target material B |
x1, x2, x3 | y1, y2, y3 | Model-derived descriptor (method-dependent) | Comparative evaluation across same dataset structure |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.