

Submitted:
10 September 2026
Posted:
11 September 2026
You are already at the latest version
Abstract
Chimeric antigen receptor (CAR) T-cell therapy for solid tumors is limited by inadequate T-cell persistence and tumor infiltration, as well as treatment-associated cytokine release syndrome (CRS). To address these challenges, we developed a metabolically rewired CAR T-cell (MRCAR) platform by co-expressing adenosine deaminase 1 (ADA1) and CD26 in CAR T cells. MRCAR T cells were generated using either GPC3-targeted CARs for hepatocellular carcinoma (HCC) or HER2-targeted CARs for breast cancer. For HCC, we further evaluated constructs with and without enforced IL-15 expression to boost T-cell function. In vitro, IL-15–expressing GPC3-MRCAR T cells exhibited enhanced proliferation, sustained effector function, reduced exhaustion, and superior cytotoxicity following repeated antigen stimulation compared with conventional CAR T cells. CD26 expression significantly enhanced CAR T-cell invasiveness in transwell assays and promoted tumor infiltration in vivo in both tumor models. ADA1 expression enhanced CAR T-cell persistence and was associated with increased frequencies of memory and stem-like T-cell populations in vivo. Notably, although IL15-GPC3-CAR T-cell treatment increased antitumor activity, it also caused high mortality and systemic inflammation in in Huh7 tumor-bearing mice, whereas incorporation of ADA1 and CD26 into MRCAR T cells significantly improved survival and reduced serum levels of IL-6, IFN-γ, and TNF-α. Mechanistically, conventional IL-15–expressing GPC3-CAR T cells induced proinflammatory M1-like macrophage activation, whereas MRCAR T cells markedly suppressed this inflammatory response. Collectively, these results indicate that metabolic rewiring via ADA1 and CD26 enhances CAR T-cell expansion, tumor infiltration, persistence, and safety, supporting the MRCAR platform as a promising strategy to improve both efficacy and tolerability of CAR T-cell therapy for solid tumors.
Keywords:
CAR T cell
; IL-15
; ADA1
; CD26
; solid tumor
; persistence
; invasion
; cytokine release syndrome
; inflammation
; memory T cells
; macrophage polarization
1. Introduction
Adoptive cell therapies employing chimeric antigen receptor (CAR) T cells have transformed the treatment landscape for hematologic malignancies, providing unprecedented rates of durable remissions in diseases such as acute lymphoblastic leukemia and diffuse large B-cell lymphoma (1-7). Despite these successes, CAR T cell therapy in solid tumors remains largely ineffective due to major barriers, including insufficient T cell persistence, limited tumor infiltration, rapid functional exhaustion, and the risk of severe cytokine release syndrome (CRS) (8, 9). The immunosuppressive microenvironment of solid tumors, characterized by poor nutrient availability, high concentrations of inhibitory metabolites such as adenosine, and the presence of immunosuppressive myeloid cells, greatly impedes CAR T cell functionality (10-18).
To overcome these obstacles, recent efforts have focused on modifying CAR T cell metabolism, differentiation, and migratory capacity. Strategies to improve T cell persistence, such as engineering cytokine signaling (e.g., IL-15 expression), enhancing memory phenotypes, and increasing resistance to exhaustion, have yielded incremental improvements (19, 20). However, potent CAR T cell expansion often comes at the cost of increased risk for CRS, driven by excessive pro-inflammatory cytokine release (20). Thus, achieving enhanced anti-tumor efficacy without escalating toxicity remains a primary goal in the clinical translation of CAR T cell therapy for solid tumors.
Adenosine deaminase 1 (ADA1) is a central enzyme in purine metabolism that catalyzes the conversion of adenosine, an immunosuppressive metabolite abundant in solid tumors, into inosine, thereby restoring T cell metabolic fitness and effector functions (21-24). ADA1 activity has been implicated in alleviating adenosine-mediated suppression and supporting tumor-specific immune responses (12, 14, 25-27). Furthermore, CD26 (dipeptidyl peptidase 4) is recognized for its role in T cell migration, invasion, and survival; CD26high T cell subsets exhibit enhanced tumor infiltration, persistence, and memory formation (28). The co-expression of ADA1 and CD26, therefore, offers a compelling avenue to simultaneously improve CAR T cell expansion, infiltration, and metabolic resistance within the hostile tumor microenvironment(14, 15).
Here, we present a new generation of multi-receptor CAR T cells, termed MRCAR, that combine the tumor targeting specificity of GPC3- and HER2-directed CARs with IL-15-mediated proliferative support and metabolic rewiring through ADA1 and CD26 co-expression. We systematically evaluate the functional impact of ADA1–CD26 axis on CAR T cell proliferation, cytotoxicity, exhaustion, invasion, and persistence in preclinical models of hepatocellular carcinoma (HCC) and breast cancer. Mechanistically, we show that ADA1 suppresses systemic toxicity by attenuating pro-inflammatory cytokine production and promoting beneficial macrophage polarization. CD26 enhances the invasive capacity of CAR T cells and facilitates tumor infiltration. Together, ADA1–CD26 rewiring confers remarkable improvements in anti-tumor efficacy and safety, providing a blueprint for the clinical development of CAR T cell therapies targeting solid tumors.
2. Methods
Cell Lines and Cell Culture
The HEK293T and HepG2 cell lines were obtained from the American Type Culture Collection (ATCC). BT-474, SUM159, MDA-MB-231, and MDA-MB-468 tumor cell lines were kindly provided by Dr. Jin Wang (Baylor College of Medicine, Houston, TX). T47D and MCF7 cells were kindly provided by Dr. Xia Gao (Baylor College of Medicine, Houston, TX). All cell lines were cultured in Dulbecco’s modified Eagle medium (DMEM; Corning) supplemented with 10% fetal bovine serum (FBS; Gibco) and maintained under standard cell culture conditions.
Primary Human T Cell Isolation and Transduction
Human peripheral blood mononuclear cells (PBMCs) purchased from STEMCELL Technologies (70025) were stimulated for 48 h on plates coated with OKT3 (Miltenyi Biotec, 130-093-387) and anti-CD28 (BD Pharmingen, 567117) monoclonal antibodies in RPMI-1640 medium (Corning) supplemented with 10% FBS (Gibco) and 100 U/mL IL-2 (PeproTech, 200-02). After 48 h of stimulation, the cells were transduced on Retronectin-coated (Takara, T100A) plates preloaded with retroviral particles. Following 48 h of transduction, the cells were removed from the plates, washed, and cultured in complete RPMI-1640 medium supplemented with IL-2 for further expansion.
Flow Cytometry
An Alexa Fluor 647-conjugated anti-F(ab′)₂ antibody (Jackson ImmunoResearch, 115-605-006) was used to detect GPC3-CAR expression. Alexa Fluor 647-conjugated HER2 protein (Bio-Techne, AFR1129) was used to detect HER2 expression. The antibodies used for T-cell phenotyping and exhaustion analyses included CD3-BV785 (BioLegend, 317329), CD45RA-BV570 (BioLegend, 304131), CCR7-APC (BioLegend, 353213), CD62L-BV711 (BioLegend, 304859), CD26-FITC (BD Biosciences, 555436), PD-1-APC (BioLegend, 329908), LAG-3-Pacific Blue (BioLegend, 369341), TIM-3-PE (BD Biosciences, 565570), and TIGIT-AF700 (R&D Systems, FAB7898N). Additional antibodies included CD80-BV605 (BioLegend, 305227), HLA-DR-FITC (BioLegend, 361706), CD163-BV711 (BioLegend, 333630), CD206-Alexa Fluor 647 (BioLegend, 321116), and HER2-Alexa Fluor 647 (BioLegend, 324412). Flow cytometry data were acquired using a Cytek Aurora Spectral Analyzer (Cytek Biosciences) and analyzed using FlowJo software (Tree Star).
IL-15 ELISA and ADA1 Activity Assays
To measure IL-15 concentration, the Human IL-15 ELISA Kit (R&D Systems, Cat. No. D1500) was used according to the manufacturer’s instructions. Cell culture supernatants were collected, centrifuged, and stored frozen until analysis. For determination of ADA activity, cells were cultured at a density of 2 × 10⁶ cells/mL in 12-well plates for 24 h. Cell culture supernatants and cells were then collected for ADA activity analysis. ADA activity was measured using the Adenosine Deaminase Activity Assay Kit (Elabscience, Cat. No. E-BC-K197-M) according to the manufacturer’s instructions.
In Vitro Cytotoxicity Assays
The cytotoxicity of CAR T cells was evaluated using an LDH release assay. GPC3-CAR T cells were co-cultured with Huh7 cells, whereas HER2-CAR T cells were co-cultured with BT-474, T47D, MCF7, SUM159, MDA-MB-231, or MDA-MB-468 tumor cells at the indicated effector-to-target (E:T) ratios. After 4 or 18 h of co-culture, cell culture supernatants were collected, and LDH release was measured using the LDH Cytotoxicity WST Assay (ENZO, Cat. No. ENZ-KIT157) according to the manufacturer’s instructions.
Repeated Tumor Stimulation and Exhaustion Marker Assessment
CAR T cells were repeatedly co-cultured with fresh Huh7 or HepG2 tumor cells at a 1:1 effector-to-target (E:T) ratio. After 3 days of co-culture, non-adherent CAR T cells were collected, counted, and re-stimulated with fresh target cells at the same 1:1 E:T ratio. This process was repeated for a total of three rounds of tumor stimulation. At the end of each co-culture interval, CAR T cells were harvested for assessment of cell viability and phenotype. Annexin V staining was performed using the ApoScreen Annexin V Apoptosis Kit (SouthernBiotech, Cat. No. 10010-09) according to the manufacturer’s instructions. The expression of exhaustion-associated markers, including LAG-3, PD-1, TIGIT, and TIM-3, were assessed by flow cytometry after each round of tumor stimulation.
CFSE Proliferation Assay
CAR T-cell proliferation was assessed using the Carboxyfluorescein Diacetate Succinimidyl Ester (CFSE) Cell Division Tracking Kit (BioLegend, Cat. No. 423801). CAR T cells were labeled with CFSE according to the manufacturer’s instructions and co-cultured with Huh7 cells at 1:1 ratio for 3 days. Following co-culture, CAR T cells were collected and analyzed by flow cytometry. T-cell proliferation was quantified based on the progressive dilution of CFSE fluorescence resulting from cell division.
Mitochondrial Membrane Potential Analysis
Mitochondrial membrane potential was assessed using the MitoProbe™ TMRM Kit for Flow Cytometry (Thermo Fisher Scientific, Cat. No. M20036) according to the manufacturer’s instructions. Briefly, cells were resuspended in PBS and stained with TMRM at a final concentration of 20 nM and incubated for 30 min at 37°C in 5% CO₂, protected from light. Following staining, cells were optionally washed once and resuspended in PBS. TMRM fluorescence was measured by flow cytometry using 561-nm excitation and a PE-equivalent emission filter.
HER2-ADC Resistance Assay
To evaluate the sensitivity of tumor cells to HER2 antibody–drug conjugate (HER2-ADC), each tumor cell line was treated with HER2-ADC (MedChemExpress, Cat. No. HY-138298) at concentrations of 0, 0.1, 1, or 10 µg/mL. After 3 or 5 days of incubation, cell viability was assessed using the Cell Counting Kit-8 (CCK-8) assay (Boster, Cat. No. AR1160) according to the manufacturer’s instructions.
Transwell Invasion Assay
24-well Transwell inserts with 3.0-µm or 5.0-µm pores (Corning, Cat. No. 353096, Cat. No. 3421) were coated with Matrigel (Corning, Cat. No. 354234) and allowed to dry before reconstitution with serum-free medium. A total of 2 × 10⁵ cells were added to each Transwell insert. The inserts were placed in wells containing 0.4 mL of serum-free medium supplemented with 20 nM SDF-1α. For inhibitor studies, cells were pre-incubated for 1 h with a CD45 inhibitor (Sigma-Aldrich, 540215), p38 MAPK inhibitor SB203580 (Sigma-Aldrich, 559389), MEK1 inhibitor PD98059 (Sigma-Aldrich, 513000), or PI3K inhibitor LY294002 (Promega Corporation, V1201). After 24 h of incubation, cells that had migrated through the Matrigel-coated membrane were collected and counted using a hemocytometer. The total cell number was determined from cells cultured under the same inhibitor treatment conditions without Transwell inserts. The invasion level was calculated as the number of cells that migrated through the Matrigel-coated membrane divided by the total cell number(32-34).
RT-qPCR
Total RNA was extracted using RNeasy Plus Mini Kit (50) (Qiagen, Cat# 74134) and reverse-transcribed using qScript cDNA SuperMix (Quantabio, Cat# 95048-100). Quantitative PCR was carried out with SsoAdvanced Universal SYBR Green Supermix (Bio-Rad, Cat# 1725270) on a QuantStudio™ 6 Flex Real-Time PCR System (Thermo Fisher Scientific). The following primers were used for detection: mouse GAPDH-F (CATGGCCTTCCGTGTTCCTA) and GAPDH-R (CCTGCTTCACCACCTTCTTGAT); human HER2scfv-F (AACACGGCCTACCTGCAAAT) and HER2scfv-R (ACAGGAACTTGTGGCTCTGG).
Western Blot Analysis of SDF-1α-Induced Signaling
To assess SDF-1α-induced phosphorylation, cells were cultured overnight in serum-free medium and stimulated with SDF-1α at a final concentration of 10 nM for 2.5- or 10-min(35-37). Cells were then diluted in ice-cold PBS containing 1 mM sodium vanadate and harvested. Cells were lysed in RIPA buffer supplemented with Mini Protease Inhibitor Cocktail (Roche) and Phosphatase Inhibitor Cocktail Set (Millipore). Protein concentrations in the cell lysates were determined using the BCA Protein Assay Kit (Life Technologies, Cat. No. 23227). Equal amounts of protein were separated by 10% SDS-PAGE and transferred to PVDF membranes (Bio-Rad) using standard procedures. Membranes were probed with primary antibodies against Akt (Cell Signaling Technology, Cat. No. 9272S), phospho-Akt (Ser473) (Cell Signaling Technology, Cat. No. 9271T), p44/42 MAPK (ERK1/2) (Cell Signaling Technology, Cat. No. 9102S), and phospho-p44/42 MAPK (ERK1/2) (Cell Signaling Technology, Cat. No. 9101S).
In Vivo Tumor Models
NSG mice (NOD.Cg-Prkdc^scid Il2rg^tm1Wjl/SzJ, Jackson Labs Cat# 005557), female and male, 6–8 weeks. All animal studies were approved by the Institutional Animal Care and Use Committee (IACUC protocol #[insert]). Huh7, Huh7-Luc, or T47D tumor cells were resuspended in 100 μL of PBS and administered to mice by subcutaneous (s.c., flank) or intraperitoneal (i.p.) injection, as indicated. Tumors were allowed to establish and grow to approximately 100 mm³, after which mice were randomized into treatment groups. Mice bearing tumors in the indicated models received a single intravenous (i.v.) or intraperitoneal (i.p.) injection of the indicated number of CAR T cells. Tumor growth was monitored by caliper measurement three times per week, and tumor volume was calculated using the formula: tumor volume = (length × width²)/2. Mice were monitored daily for tumor progression and overall health throughout the study. Humane endpoints included tumor size >1.5 cm³ or signs of distress.
In Vivo Imaging
Huh7 or CAR T cells were transduced with a retroviral vector encoding enhanced firefly luciferase (effLuc), which we generated in-house as previously described (19, 20, 29). Mice received 150 mg/kg D-luciferin (GoldBio Cat# LUCNA) intraperitoneally, and bioluminescent signal was acquired using PerkinElmer Living Image software. Signal quantification used photon flux (p/s/cm²/sr); background was deducted from each ROI.
Cytokine Multiplex Analysis
Mouse serum was collected from blood on days 1, 2, and 7 after CAR T cell administration, and stored at -80ºC. Cytokine concentrations in the serum were measured in duplicate using Luminex bead-based assays (LXSAHM-09 kits, Bio-Techne, Minneapolis, USA) following the manufacturer’s instructions specific to each kit. Briefly, serum samples were thawed on ice, centrifuged, and diluted 1:2 with RD6-52. Diluted samples were incubated with beads for 2 h at room temperature with shaking, followed by incubation with Biotin-Antibody Cocktail and streptavidin-PE. Samples were analyzed using the Bio-Plex 200 system and Bio-Plex Manager 7.2 software (Bio-Rad, Hercules, CA). Fifty beads per analyte were collected with a 60-second timeout set for plate analysis. Cytokine concentrations were calculated using a standard curve with a 5-parameter logistic-fitting method in Bio-Plex manager software, and the average values of the replicates were used for the final analysis(38-40).
Macrophage Co-Culture and Polarization Assays
Human monocytes were isolated from PBMCs and differentiated to macrophages with M-CSF (50 ng/mL, PeproTech Cat# 300-25) for 7 days. To assess macrophage polarization, macrophages were polarized toward an M1-like phenotype by treatment with LPS (100 ng/mL) and IFN-γ (20 ng/mL), whereas M2 polarization was induced with IL-4 (20 ng/mL) and IL-13 (20 ng/mL). Macrophage polarization was evaluated by assessing the expression of M1-associated markers (CD80, CD86, and HLA-DR) and M2-associated markers (CD163 and CD206) by flow cytometry. Following polarization, macrophages were co-cultured with CAR T cells at E:T-1:1 ratio for 48 h.
Statistical Analysis
Results are expressed as mean ± SEM or SD as indicated. Sample sizes (n) and number of replicates are described in figure legends. Two-tailed unpaired Student’s t-test for two-group comparisons. One-way or two-way ANOVA with Tukey’s or Bonferroni post-hoc corrections for multi-group comparisons. Log-rank (Mantel–Cox) test for Kaplan–Meier survival curves. P-values <0.05 were considered significant. GraphPad Prism v9.0 was used for all analyses.
3. Results
Engineering and Functional Characterization of Multi-Receptor CAR T Cells
The immunosuppressive microenvironment of solid tumors presents multiple barriers to effective CAR T cell therapy, including poor persistence, limited expansion, and functional exhaustion. To address these challenges, we engineered multi-receptor CAR T cells (MRCAR) co-expressing adenosine deaminase 1 (ADA1), dipeptidyl peptidase 4 (CD26), and IL-15, with glypican-3 (GPC3) CARs (Fig. 1A). Retroviral transduction of primary human T cells from healthy donors resulted in robust expression of both GPC3-CAR and CD26, confirmed by flow cytometry (Fig. 1B, 1C). IL-15 was readily detected in supernatants of GPC3-IL15-MR CAR T cell cultures (Fig. 1D). ADA enzymatic activity assays demonstrated that MR CAR T cells secreted higher levels of ADA, which in turn bound to the surface of CAR T cells, as observed in our previous studies (19, 29). Compared to control conditions, there was a clear increase in ADA activity associated with MR CAR T cells, indicating enhanced ADA binding to the cell surface (p<0.001, Fig. 1E).
Figure 1.
Molecular and functional characterization of IL15-GPC3-MRCAR T cells with ADA1 and CD26 co-expression. (A) Schematic illustration of the IL15-GPC3-MR CAR T-cell engineering strategy. CAR T cells were generated using a two-vector retroviral transduction system consisting of a CAR vector and a separate MR retroviral vector encoding CD26 and ADA1-CD3scFv. (B) Representative flow cytometric analysis of GPC3-CAR expression in NT (non-transduced), GPC3, GPC3-MR, IL15-GPC3, and IL15-GPC3-MR CAR T-cell products following retroviral transduction. (C) Representative flow cytometric analysis of CD26 expression in the indicated CAR T-cell products. (D) CAR T cells were co-cultured with or without Huh7 cells at an effector-to-target ratio of 1:1 for 48 h. IL-15 levels in the culture supernatants were quantified by ELISA. (E) IL15-GPC3 CAR T cells transduced with or without the MR vector (2 ×10⁶ cells/ml) were cultured for 24 h. Culture supernatants and cells were then analyzed for ADA enzyme activity according to the manufacturer’s instructions (n=3). (F) The cytotoxic activity of CAR T cells against Huh7 cells at a 1:1 E:T ratio was evaluated using an LDH release assay at 4 and 18 h (mean ± SEM, n = 3). (G) Cytotoxicity was further assessed after 4 h of coculture at increasing E:T ratios of 1:1, 5:1, 10:1, and 20:1. (H) CAR T cells were expanded in vitro, and cell numbers were determined at indicated time points using a hemocytometer. Cell expansion was presented as a growth curve. (mean ± SEM, n=3). (I) CAR T cells were labeled with CFSE and co-cultured with Huh7 cells at a 1:1 E:T ratio for 3 days. CAR T-cell proliferation was then assessed by flow cytometry based on CFSE dilution.
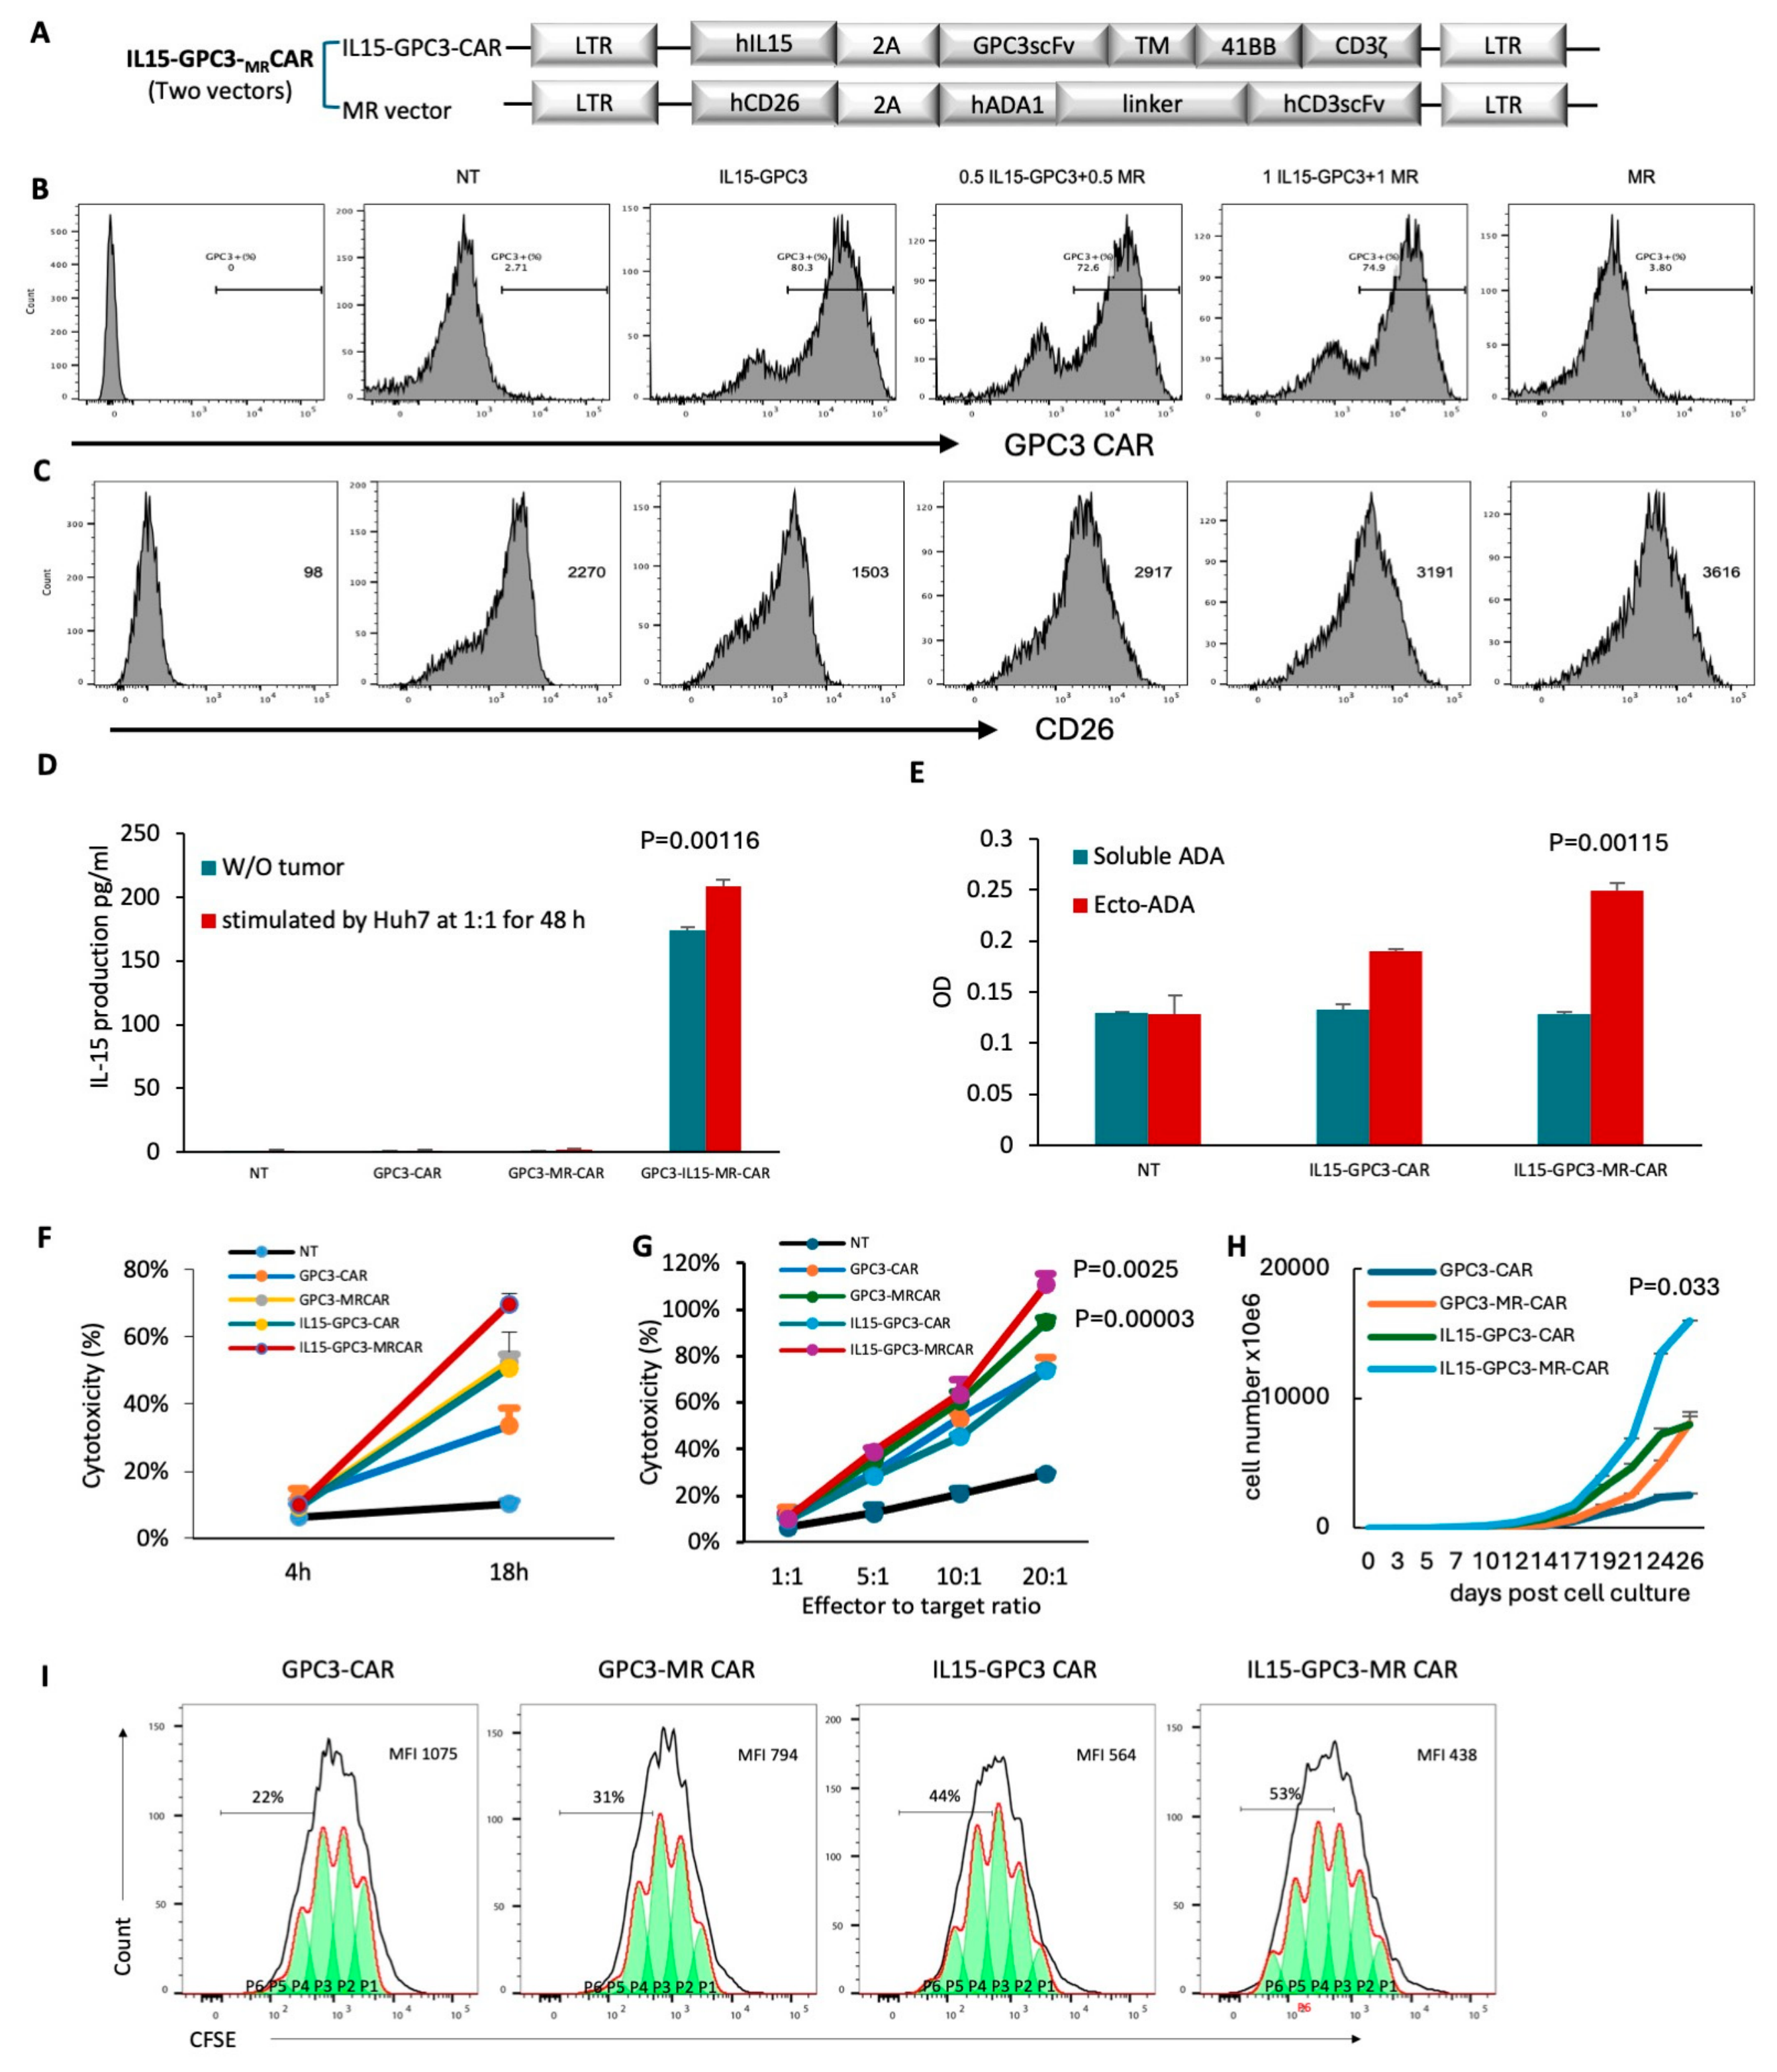
In functional assays, MR CAR T cells demonstrated significantly greater cytotoxicity than conventional CAR T cells at an E:T ratio of 1:1 following 18 hours of coculture with Huh7 cells (Fig. 1F). Enhanced cytotoxicity was evident across a range of effector-to-target ratios (Fig. 1G), confirming that metabolic and migratory rewiring supports robust expansion and anti-tumor function. While IL15 expression enhanced the expansion of GPC3 CAR T cells, incorporation of the MR module further promoted CAR T-cell expansion, resulting in markedly greater expansion compared with conventional CAR T cells (p<0.05, Fig. 1H). CFSE-based proliferation assays further demonstrated enhanced division of MR CAR T cells (p<0.01, Fig. 1I).
ADA1–CD26 MRCAR T Cells Resist Functional Exhaustion Following Repeated Tumor Antigen Stimulation
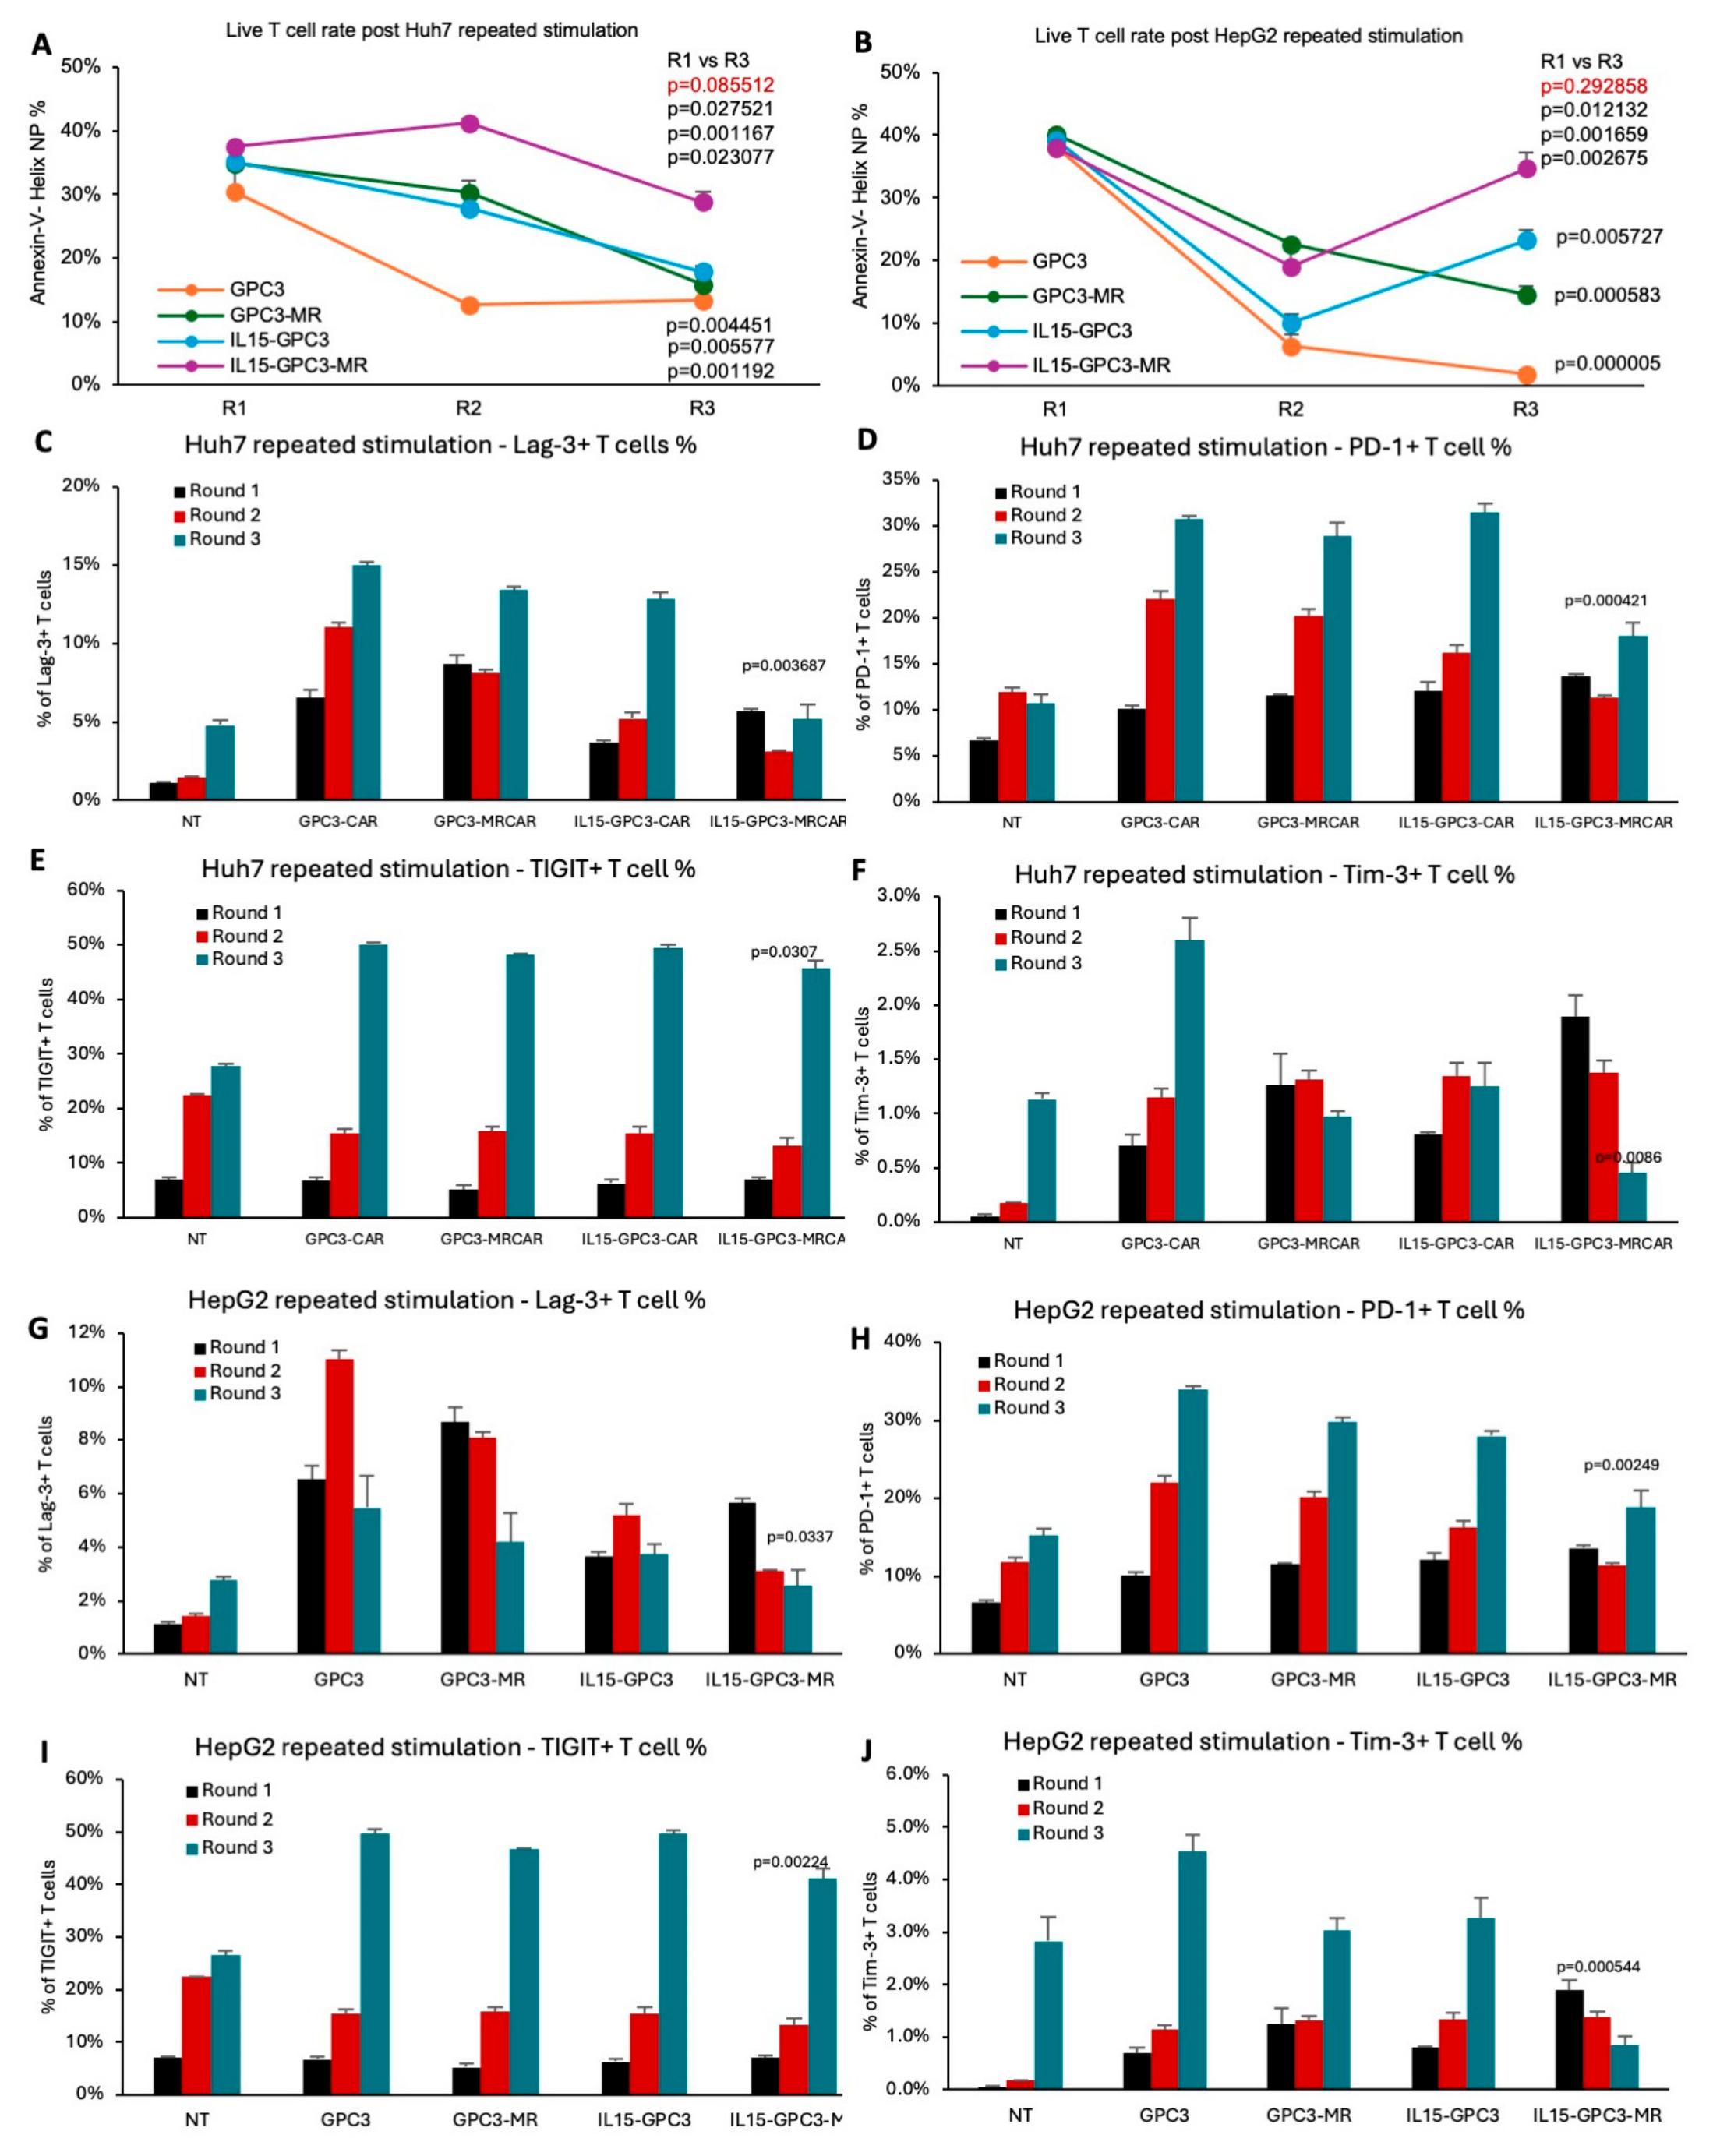
To determine whether co-expression of ADA1 and CD26 could preserve CAR T cell fitness under conditions of sustained antigen stimulation, MRCAR T cells and conventional CAR T cells were subjected to three consecutive rounds of co-culture with Huh7 or HepG2 hepatocellular carcinoma cells. Following each round of tumor-cell exposure, viable T cells were recovered and evaluated to assess their capacity to withstand repeated antigenic challenge. MRCAR T cells demonstrated substantially greater persistence throughout serial stimulation (Fig. 2A, B). The progressive preservation of viable T cells in the MRCAR T cell group suggests that ADA1–CD26 expression may protect against the cumulative loss of cellular fitness associated with chronic antigen exposure. In contrast, conventional CAR T cells exhibited a pronounced decline in viability with successive rounds of stimulation, consistent with the development of an exhausted or dysfunctional phenotype.
To characterize MRCAR T cells further, the expression of established inhibitory and exhaustion-associated receptors was examined by flow cytometry following repeated tumor-antigen stimulation. MRCAR T cells displayed markedly lower expression of LAG3, PD1, TIGIT, and TIM3 than conventional CAR T cells (all p < 0.01; Fig. 2C–F). These differences indicate that repeated antigen exposure induced a substantially weaker exhaustion-associated phenotype in MRCAR T cells. Importantly, the protective phenotype was not restricted to a single tumor model. Similar reductions in exhaustion-marker expression and improved T cell persistence were observed when MRCAR T cells were repeatedly challenged with HepG2 cells, demonstrating that the effect was reproducible across two hepatocellular carcinoma cell lines (Fig. 2G–J). Thus, the enhanced resistance of MRCAR T cells to serial antigen stimulation appears to reflect an intrinsic property of the ADA1–CD26-modified CAR T cell population rather than a tumor-cell-line-specific phenomenon.
Figure 2.
IL15-GPC3-MRCAR T cells demonstrate reduced exhaustion following repeated tumor antigen exposure in vitro. (A, B) Quantification of live CAR T cell recovery after three rounds of antigen stimulation with Huh7 (A) or HepG2 (B) cells. Data shown as percentage of live CD3^+ T cells (mean ± SEM, n=3). (C–F) Expression of exhaustion markers LAG-3 (C), PD-1 (D), TIGIT (E), and TIM-3 (F) in CAR T cells after Huh7 stimulation, measured by flow cytometry. (G–J) Same exhaustion marker analysis after repeated exposure to HepG2 cells (mean ± SEM, n=3). MRCAR T cells exhibited significantly lower exhaustion marker expression versus conventional CAR T cells (p < 0.05, Student’s t-test).
CD26 Expression Enhances CAR T Cell Tumor Invasion Through MAPK and PI3K Pathways
Since CD26 has been implicated in T cell migration, we assessed its impact on CAR T cell invasiveness in vitro and in vivo. In Matrigel-coated transwell assays, GPC3-targeted MRCAR T cells, which exhibited higher levels of CD26 expression, demonstrated significantly greater invasive activity in response to SDF-1α compared with conventional CAR T cells (p<0.01, Fig. 3A). Parallel migration enhancement was noted for HER2-targeted MRCAR T cells (Fig. 3B).
Figure 3.
CD26 expression enhances CAR T cell invasion via MAPK and PI3K signaling. (A, B) Transwell invasion assays were performed using IL15-GPC3-CAR T cells (A) and HER2-CAR T cells (B). The percentage of invasion was calculated as the number of cells that migrated through the Transwell membrane divided by the total cell number (mean ± SEM, n=3). (C) Western blotting showed that SDF-1α induced phosphorylation of signaling proteins in CAR T cells. CAR T cells were incubated with SDF-1α, and the activation of signaling kinases was assessed by measuring their phosphorylation levels. (D–G) IL15-GPC3 CAR T-cell invasion was assessed following pretreatment with kinase inhibitors. Cells were incubated with the indicated inhibitors for 1 h before the initiation of the invasion assay. The CD45 inhibitor (D) was used at 6 μM, the p38 MAPK inhibitor SB203580 (E) at 10 μM, and the MEK1 inhibitor PD98059 (F) and PI3K inhibitor LY294002 (G) at 50 μM. (H–K) HER2-CAR T-cell invasion was assessed following the same inhibitor treatments.
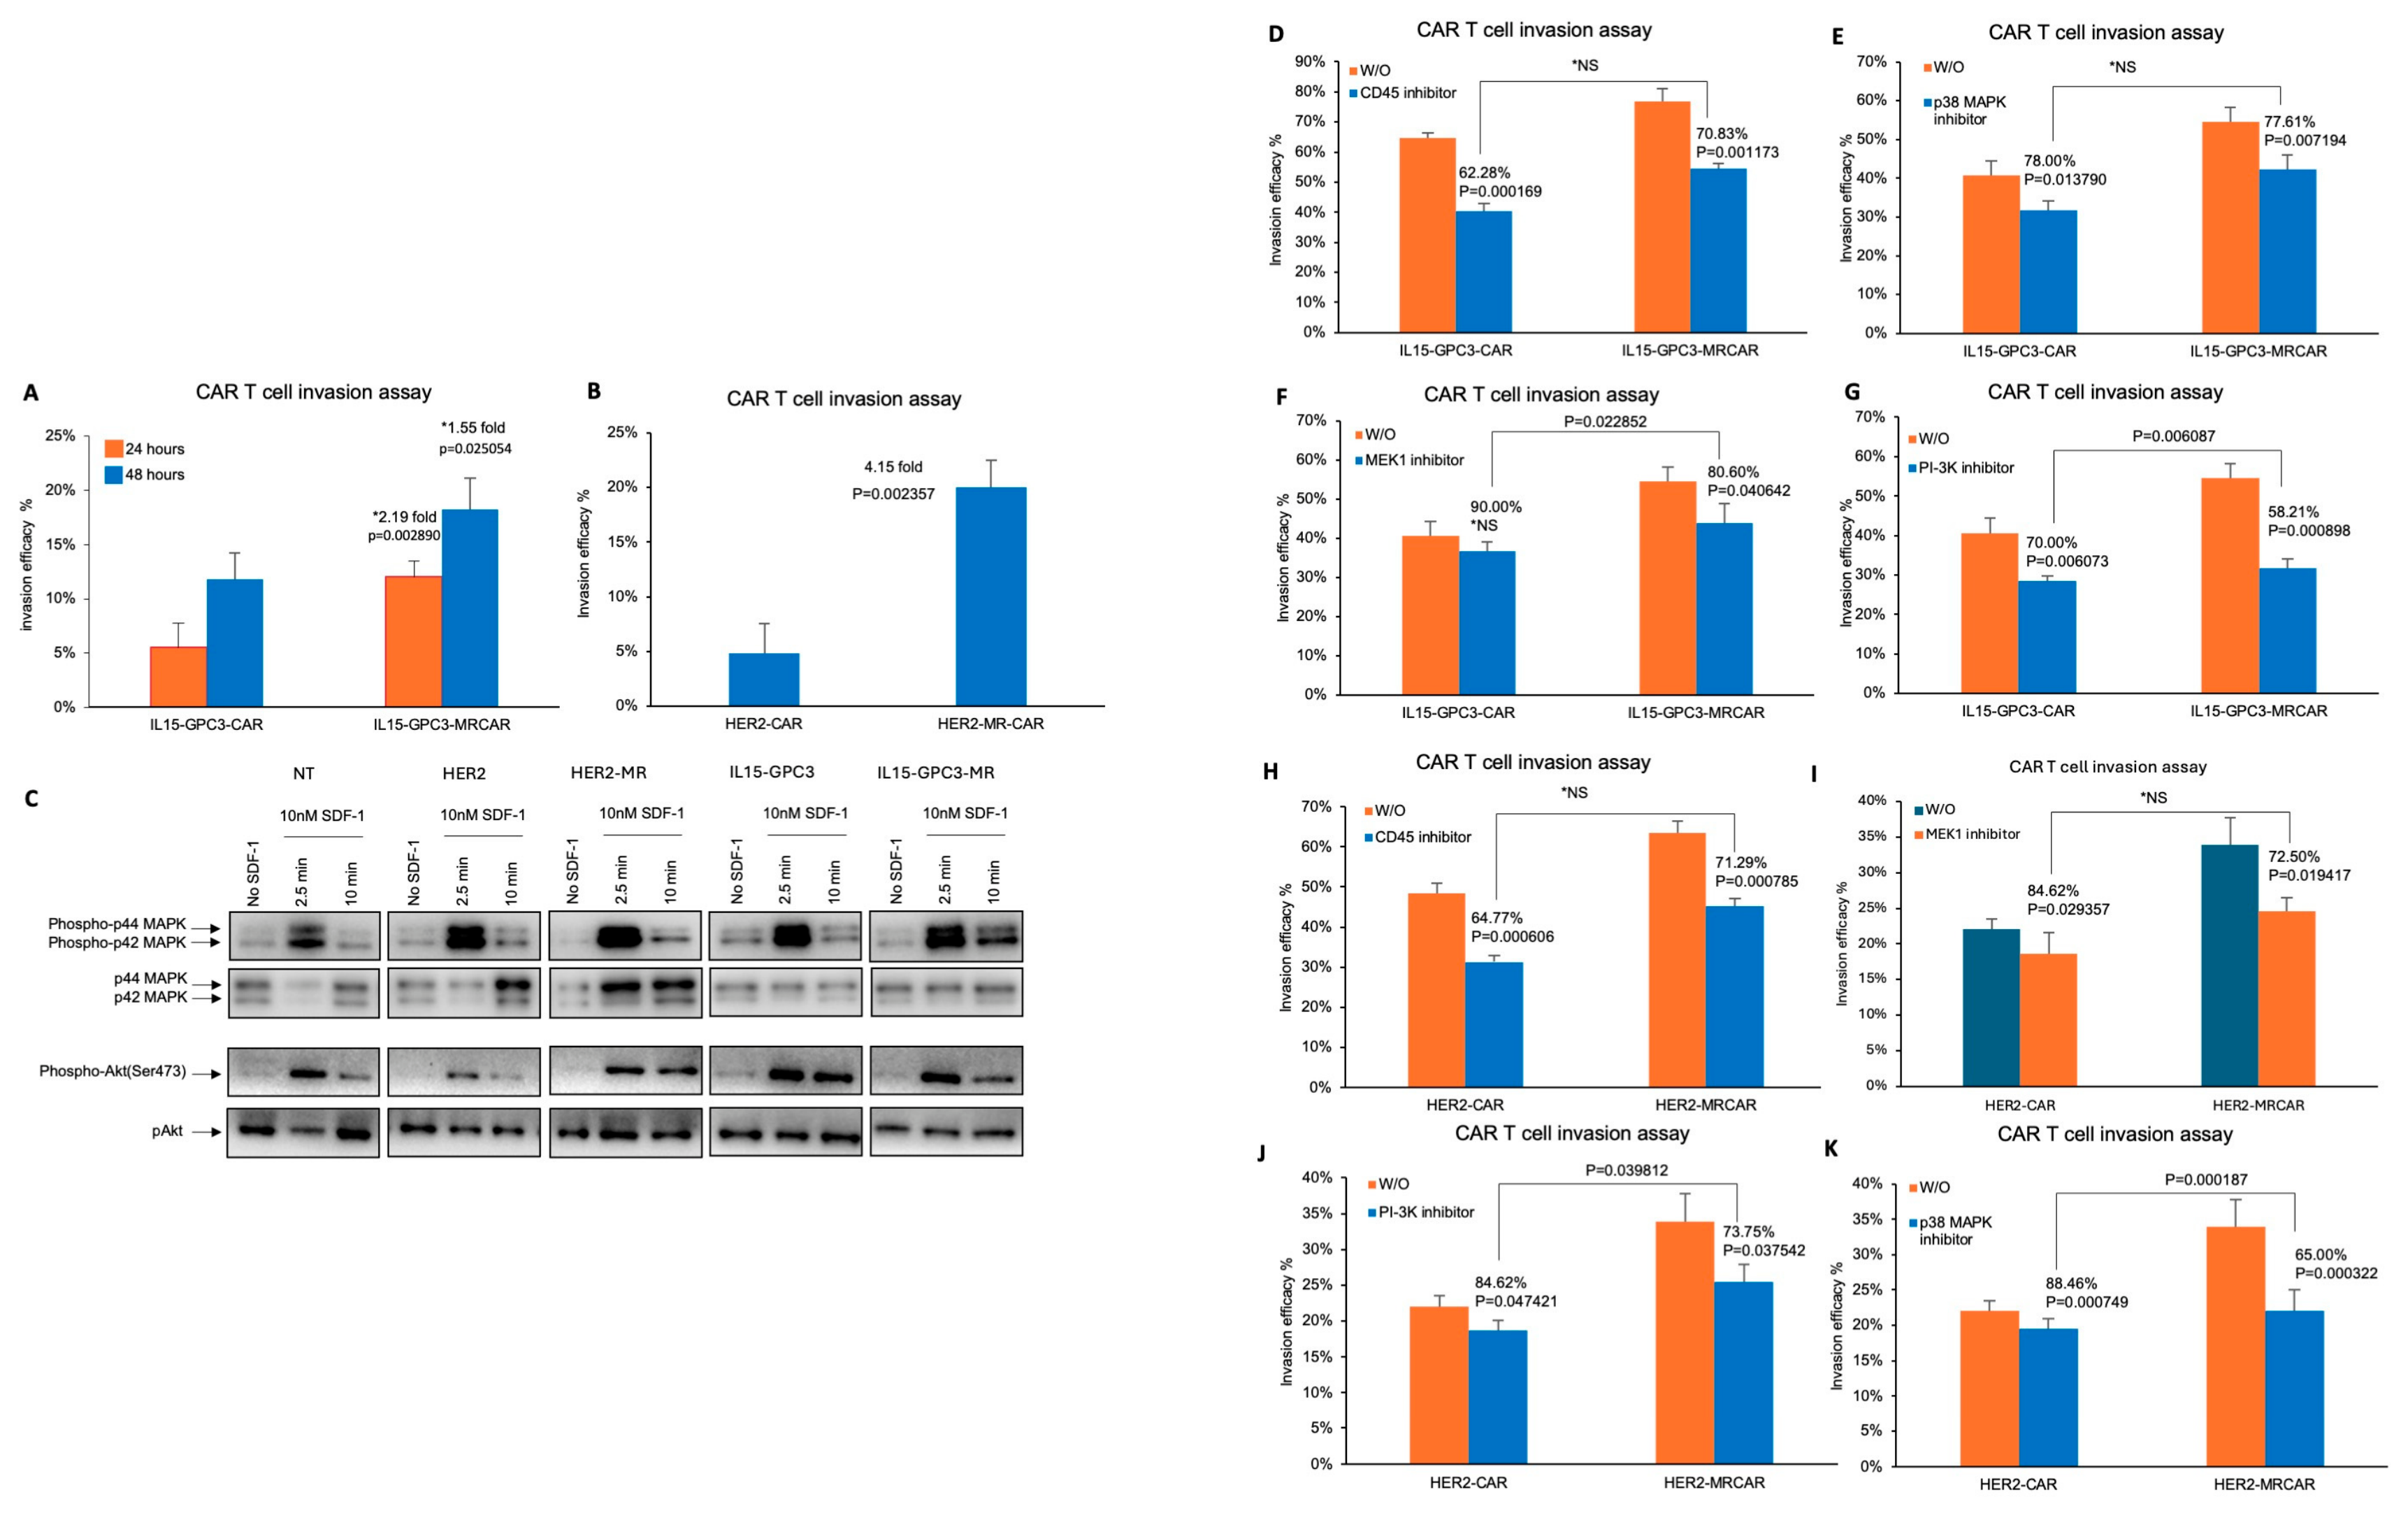
Phosphorylation of several signaling proteins has been shown to play important roles in cell migration and invasion in various cell types(35, 41, 42). To investigate the signaling pathways underlying CD26-regulated CAR T-cell invasion, we evaluated the phosphorylation status of Akt and p44/42 MAPK (ERK1/2) following SDF-1α stimulation. CAR T cells were stimulated with SDF-1α for 2.5 or 10 min, and the phosphorylation of Akt and p44/42 MAPK was assessed by Western blotting. SDF-1α stimulation induced phosphorylation of both Akt and p44/42 MAPK in CAR T cells, with increased phosphorylation observed following stimulation compared with unstimulated cells (Fig. 3C). These findings demonstrate that SDF-1α activates the Akt and p44/42 MAPK signaling pathways in CAR T cells, suggesting that these pathways may contribute to SDF-1α-mediated CAR T-cell invasive activity.
To investigate the signaling pathways underlying CD26-mediated enhancement of CAR T cell migration, we pre-incubated CAR T cells with selective inhibitors targeting PI3K, MEK1, p38 MAPK, or CD45 and evaluated their invasive capacity in vitro (Fig. 3D-K). Inhibition of PI3K with LY294002 significantly reduced the invasive activity of both GPC3- and HER2-targeted MRCAR T cells, with a significantly greater reduction relative to their corresponding conventional CAR T cells, suggesting a conserved role for PI3K signaling in CD26-enhanced invasion. In the GPC3-targeted model, MEK1 inhibition with PD98059 similarly produced a significant differential reduction in invasion between IL15-GPC3-CAR and IL15-GPC3-MRCAR T cells, whereas inhibition of p38 MAPK or CD45 did not significantly distinguish the two cell populations. Conversely, in HER2-targeted CAR T cells, p38 MAPK inhibition significantly reduced the enhanced invasive activity of MRCAR T cells relative to conventional CAR T cells, while MEK1 and CD45 inhibition did not produce a significant differential effect. These findings suggest that PI3K signaling represents a common pathway associated with CD26-mediated CAR T-cell invasion, whereas MEK1 and p38 MAPK may contribute in a tumor antigen/CAR-dependent manner.
ADA1–CD26 Axis Promotes CAR T Cell Persistence and Tumor Control in Hepatocellular Carcinoma
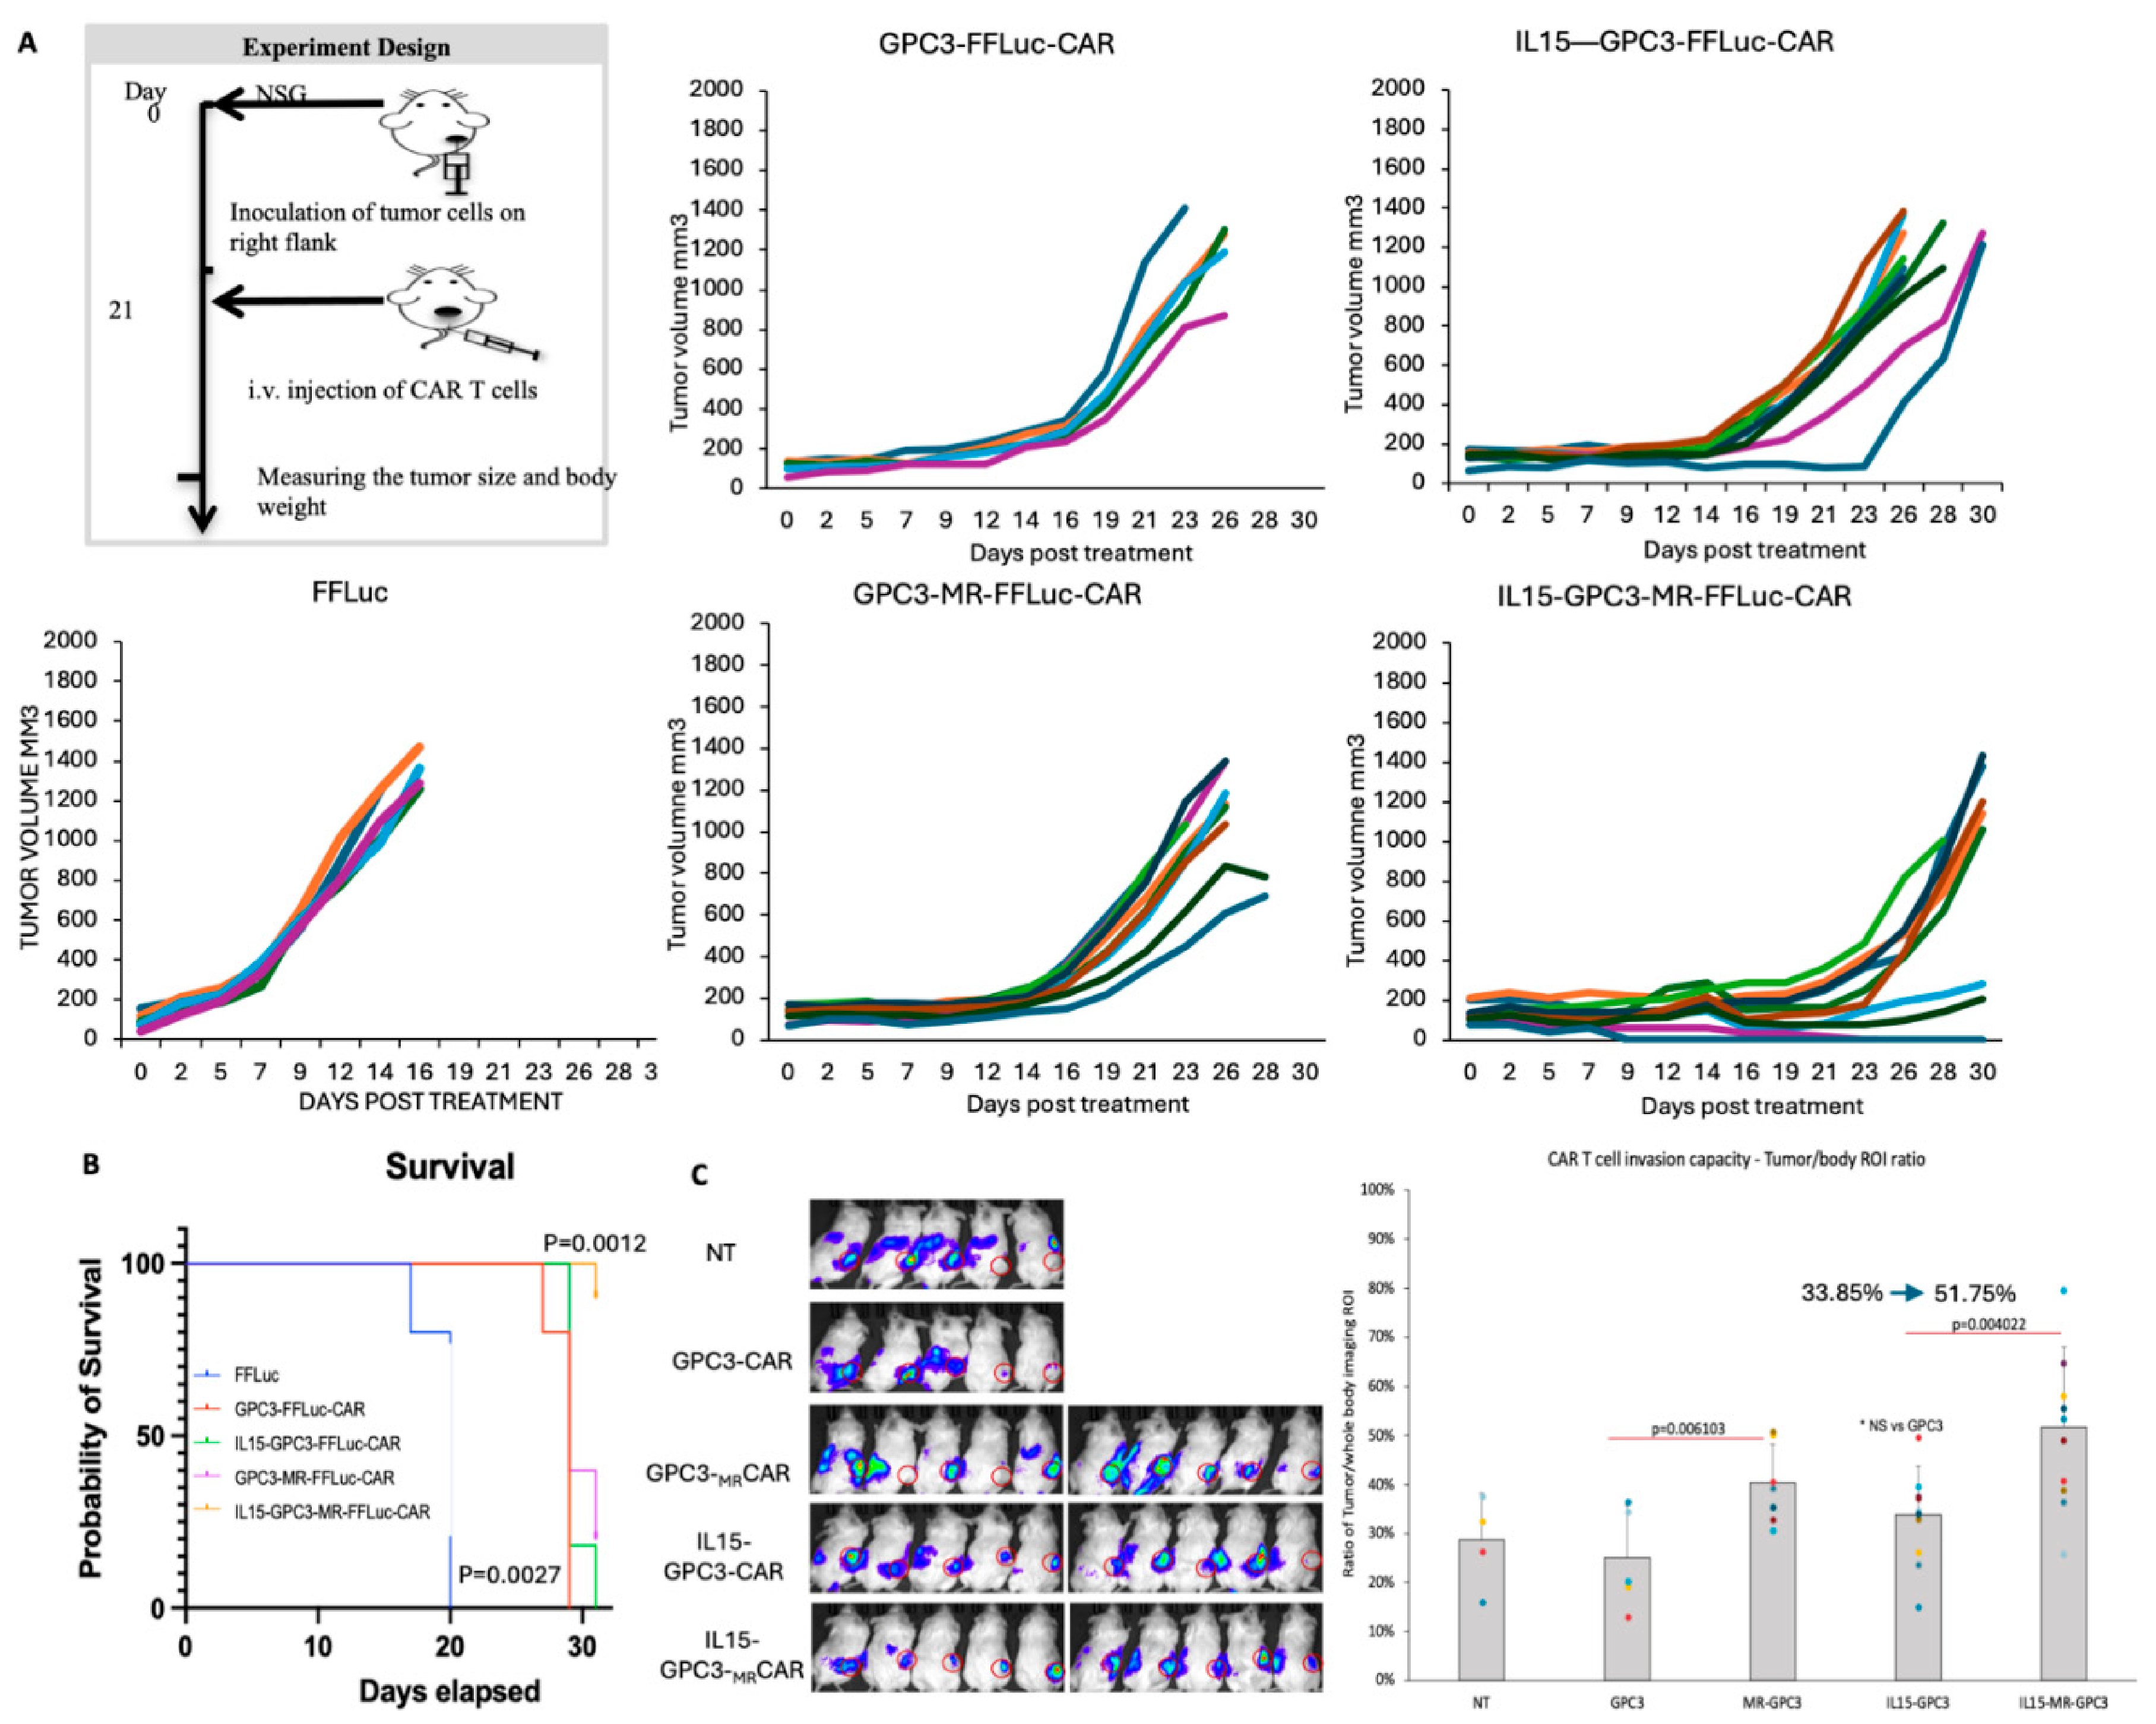
To determine whether ADA1–CD26 metabolic rewiring enhances these properties in vivo, MRCAR T cells were evaluated in a subcutaneous Huh7 xenograft model (n=5 or 10/group). MRCAR T cell treatment resulted in marked tumor regression compared with conventional CAR T cell and vehicle groups (p<0.001, Fig. 4A). Consistent with improved tumor control, MRCAR-treated mice showed significantly prolonged survival, compared to conventional CAR T cells (log-rank p<0.01, Fig. 4B).
To assess whether enhanced tumor control was associated with improved CAR T cell accumulation, tumor localization was evaluated by IVIS imaging. MRCAR T cells exhibited greater accumulation at tumor sites than conventional CAR T cells and control groups. Quantitative ROI analysis showed significantly higher tumor-associated signal in the IL15-GPC3-MR CAR T-cell group than in the conventional CAR T-cell group (p<0.01, Fig. 4C). Together, these findings indicate that ADA1–CD26 enhances CAR T cell persistence and tumor accumulation, resulting in improved antitumor efficacy and survival in HCC.
Figure 4.
ADA1–CD26 axis improves therapeutic efficacy and persistence in Huh7 hepatocellular carcinoma mouse models. A murine HCC xenograft model was established in NSG mice by subcutaneous inoculation of 2 × 10⁶ Huh7 tumor cells into the right flank. When the average tumor volume reached approximately 100 mm³, mice were treated with 1 × 10⁷ FFLuc, GPC3-FFLuc-CAR, GPC3-MR-FFLuc-CAR, IL15-GPC3-FFLuc-CAR, or IL15-GPC3-MR-FFLuc-CAR T cells. Tumor volume was monitored every 2–3 days (A). Mouse survival was monitored throughout the study (B). (C) IVIS imaging was performed to assess the infiltration of CAR T cells into tumors, and photon counts were quantified (mean ± SEM, n=5-10).
ADA1–CD26 Enables Sustained CAR T Cell Memory and Rechallenge Immunity in Breast Cancer Models
To investigate the antitumor activity of HER2-targeted MRCAR T cells, we first profiled HER2 expression across a panel of breast cancer cell lines (sFig. 1A). MRCAR T cells exhibited potent cytotoxic activity against HER2-expressing tumor cells, with cytotoxicity correlating with HER2 expression levels (sFig. 1B). Notably, the breast cancer cell lines displayed variable sensitivity to HER2-targeted antibody–drug conjugate (ADC) treatment (sFig. 1C). This heterogeneity may reflect differences in the expression of other HER family members, such as EGFR and HER3, which can form EGFR–HER2 or HER2–HER3 heterodimers and potentially alter HER2 internalization and subsequent ADC uptake(43, 44). These findings suggest that HER2 expression alone may not fully predict sensitivity to HER2-directed ADC therapy, whereas MRCAR T cells retain potent cytotoxic activity against HER2-expressing tumor cells.
Scheme 1.
HER2-CAR T cells exhibit cytotoxicity against HER2-ADC-resistant tumor cell lines. (A) Flow cytometric profiling of HER2 expression in various human breast cancer lines. (B) The cytotoxic activity of CAR T cells against breast cancer cell lines at the indicated effector-to-target ratios was evaluated using an LDH release assay 24 h after coculture (mean ± SEM, n = 3). (C) The in vitro cytotoxic effects of HER2 antibody–drug conjugate (ADC) treatment on breast cancer cell lines were evaluated using a CCK-8 assay. (mean ± SEM, n=3).
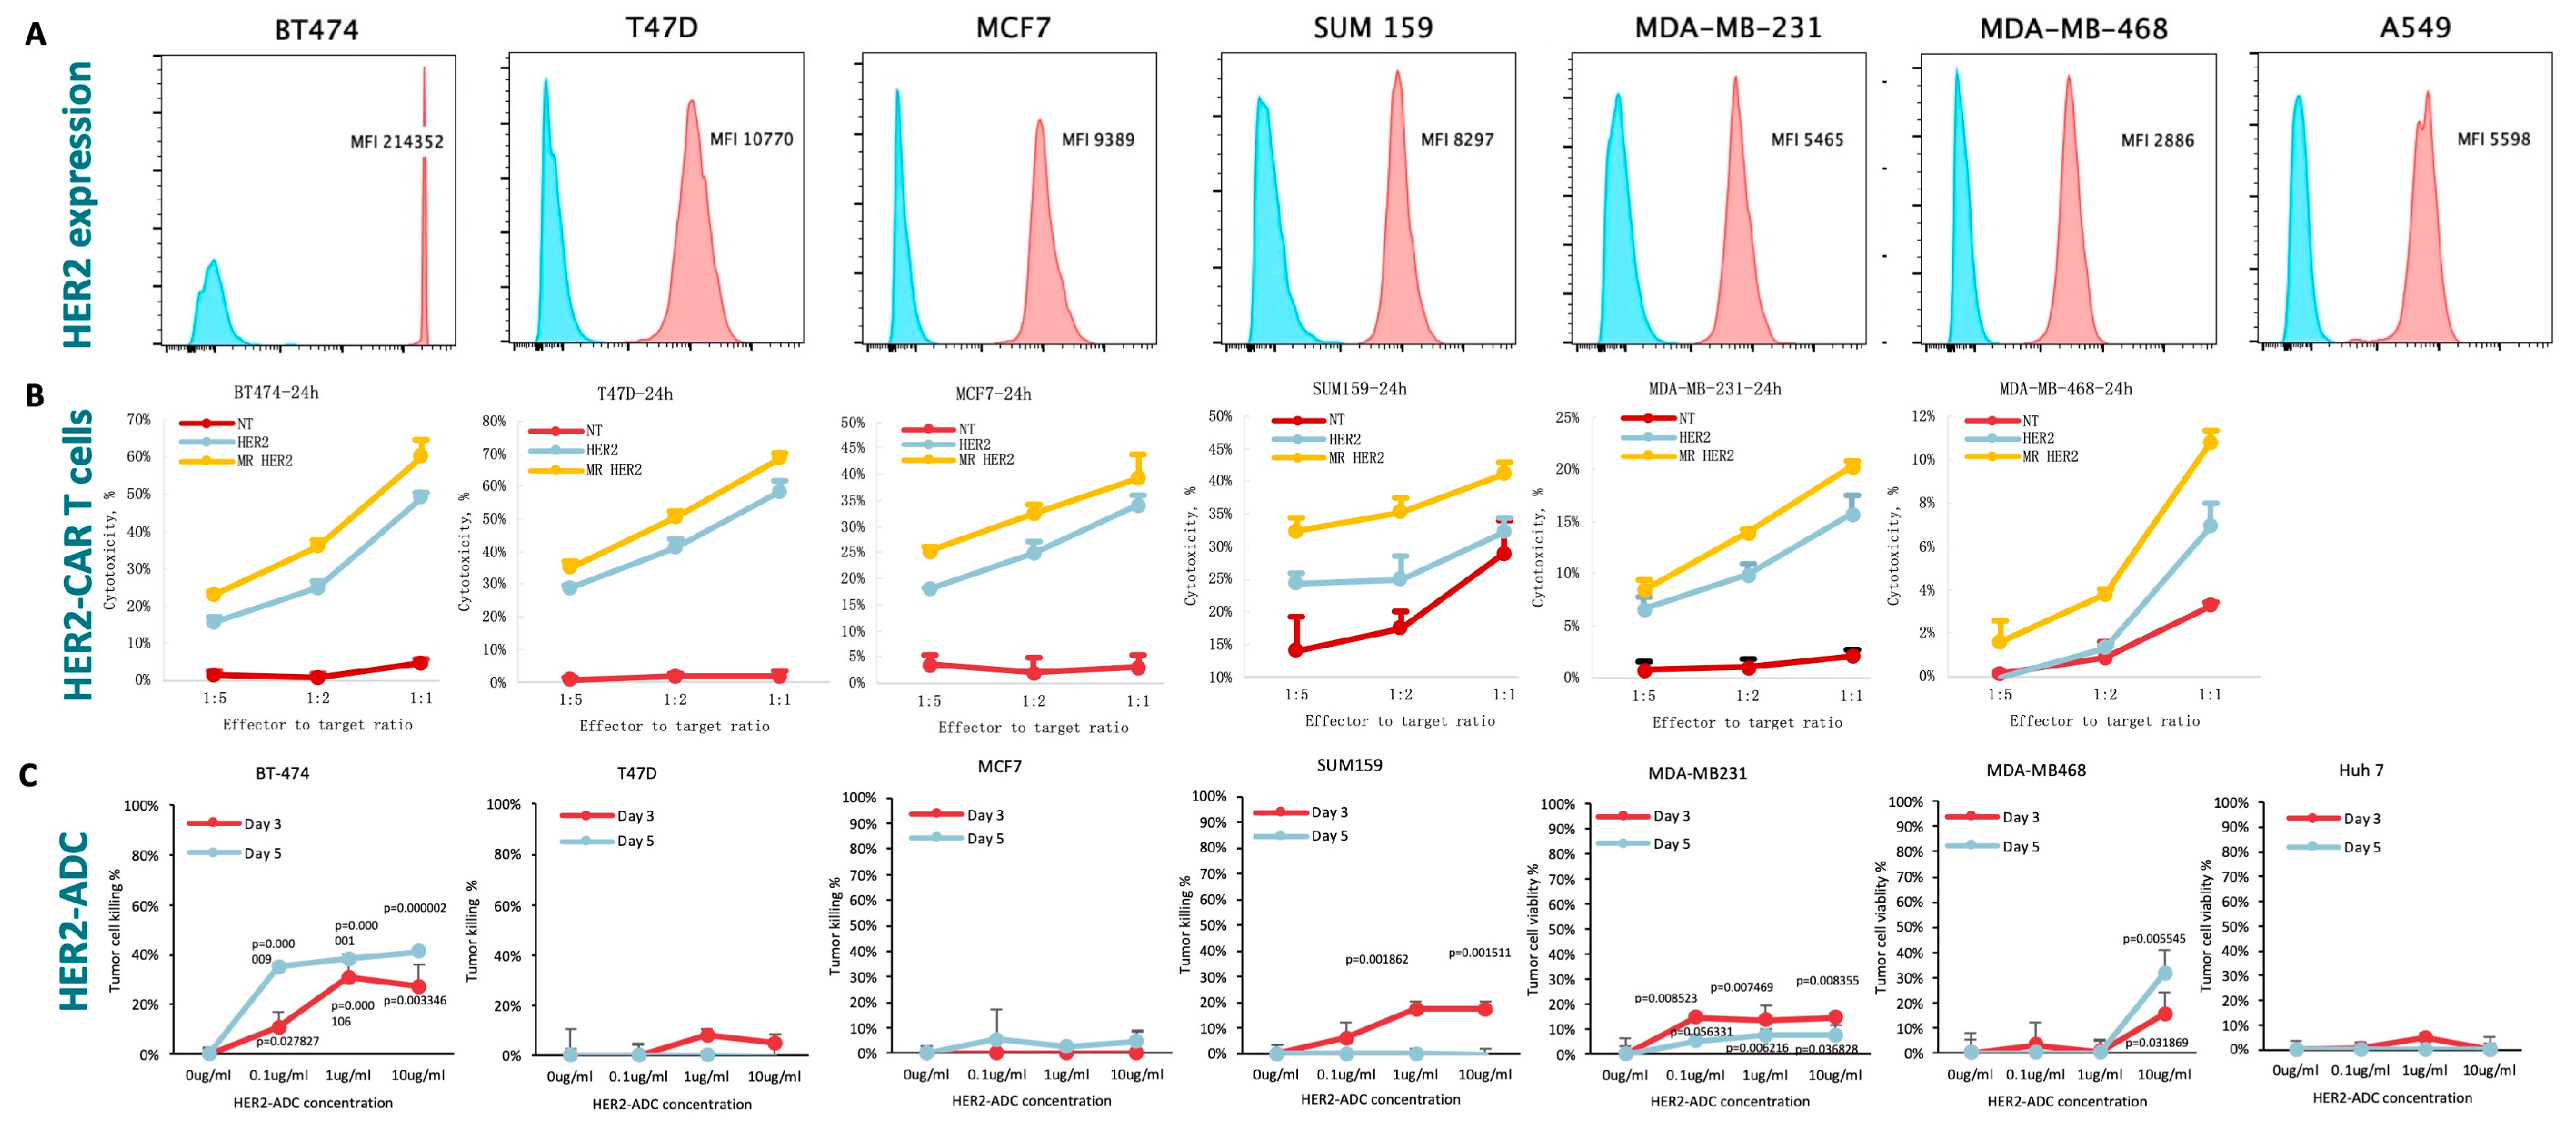
Figure 5.
ADA1–CD26 promotes CAR T cell persistence and confers tumor rechallenge protection in breast cancer models. (A) Longitudinal IVIS imaging of CAR T cell persistence in T47D breast tumor xenografts. 5 × 10⁶ T47D tumor cells were injected into the fourth mammary fat pad, followed by intravenous administration of 2 × 10⁶ FFLuc, MR-FFLuc, HER2-FFLuc, or HER2-MR-FFLuc CAR T cells (mean ± SEM, n=5 mice per group). (B) Single-cell suspensions from mouse spleens were stained and analyzed by flow cytometry to characterize T-cell subsets, including effector (Teff, CD62L⁻CCR7⁻), central memory (Tcm, CD45RA⁻CD62L⁺CCR7⁺), effector memory (Tem, CD45RA⁻CD62L⁻CCR7⁻), and stem cell-like memory (Tscm, CD45RA⁺CD62L⁺CCR7⁺) T cells. (C-D) Tissue distribution of CAR T cells in liver and lung 3 months after CAR T-cell treatment was analyzed by qPCR. (E) Tumor bearing mice curve post-CAR T therapy; n=5/group. Statistical analysis by Student’s t-test; p < 0.05.
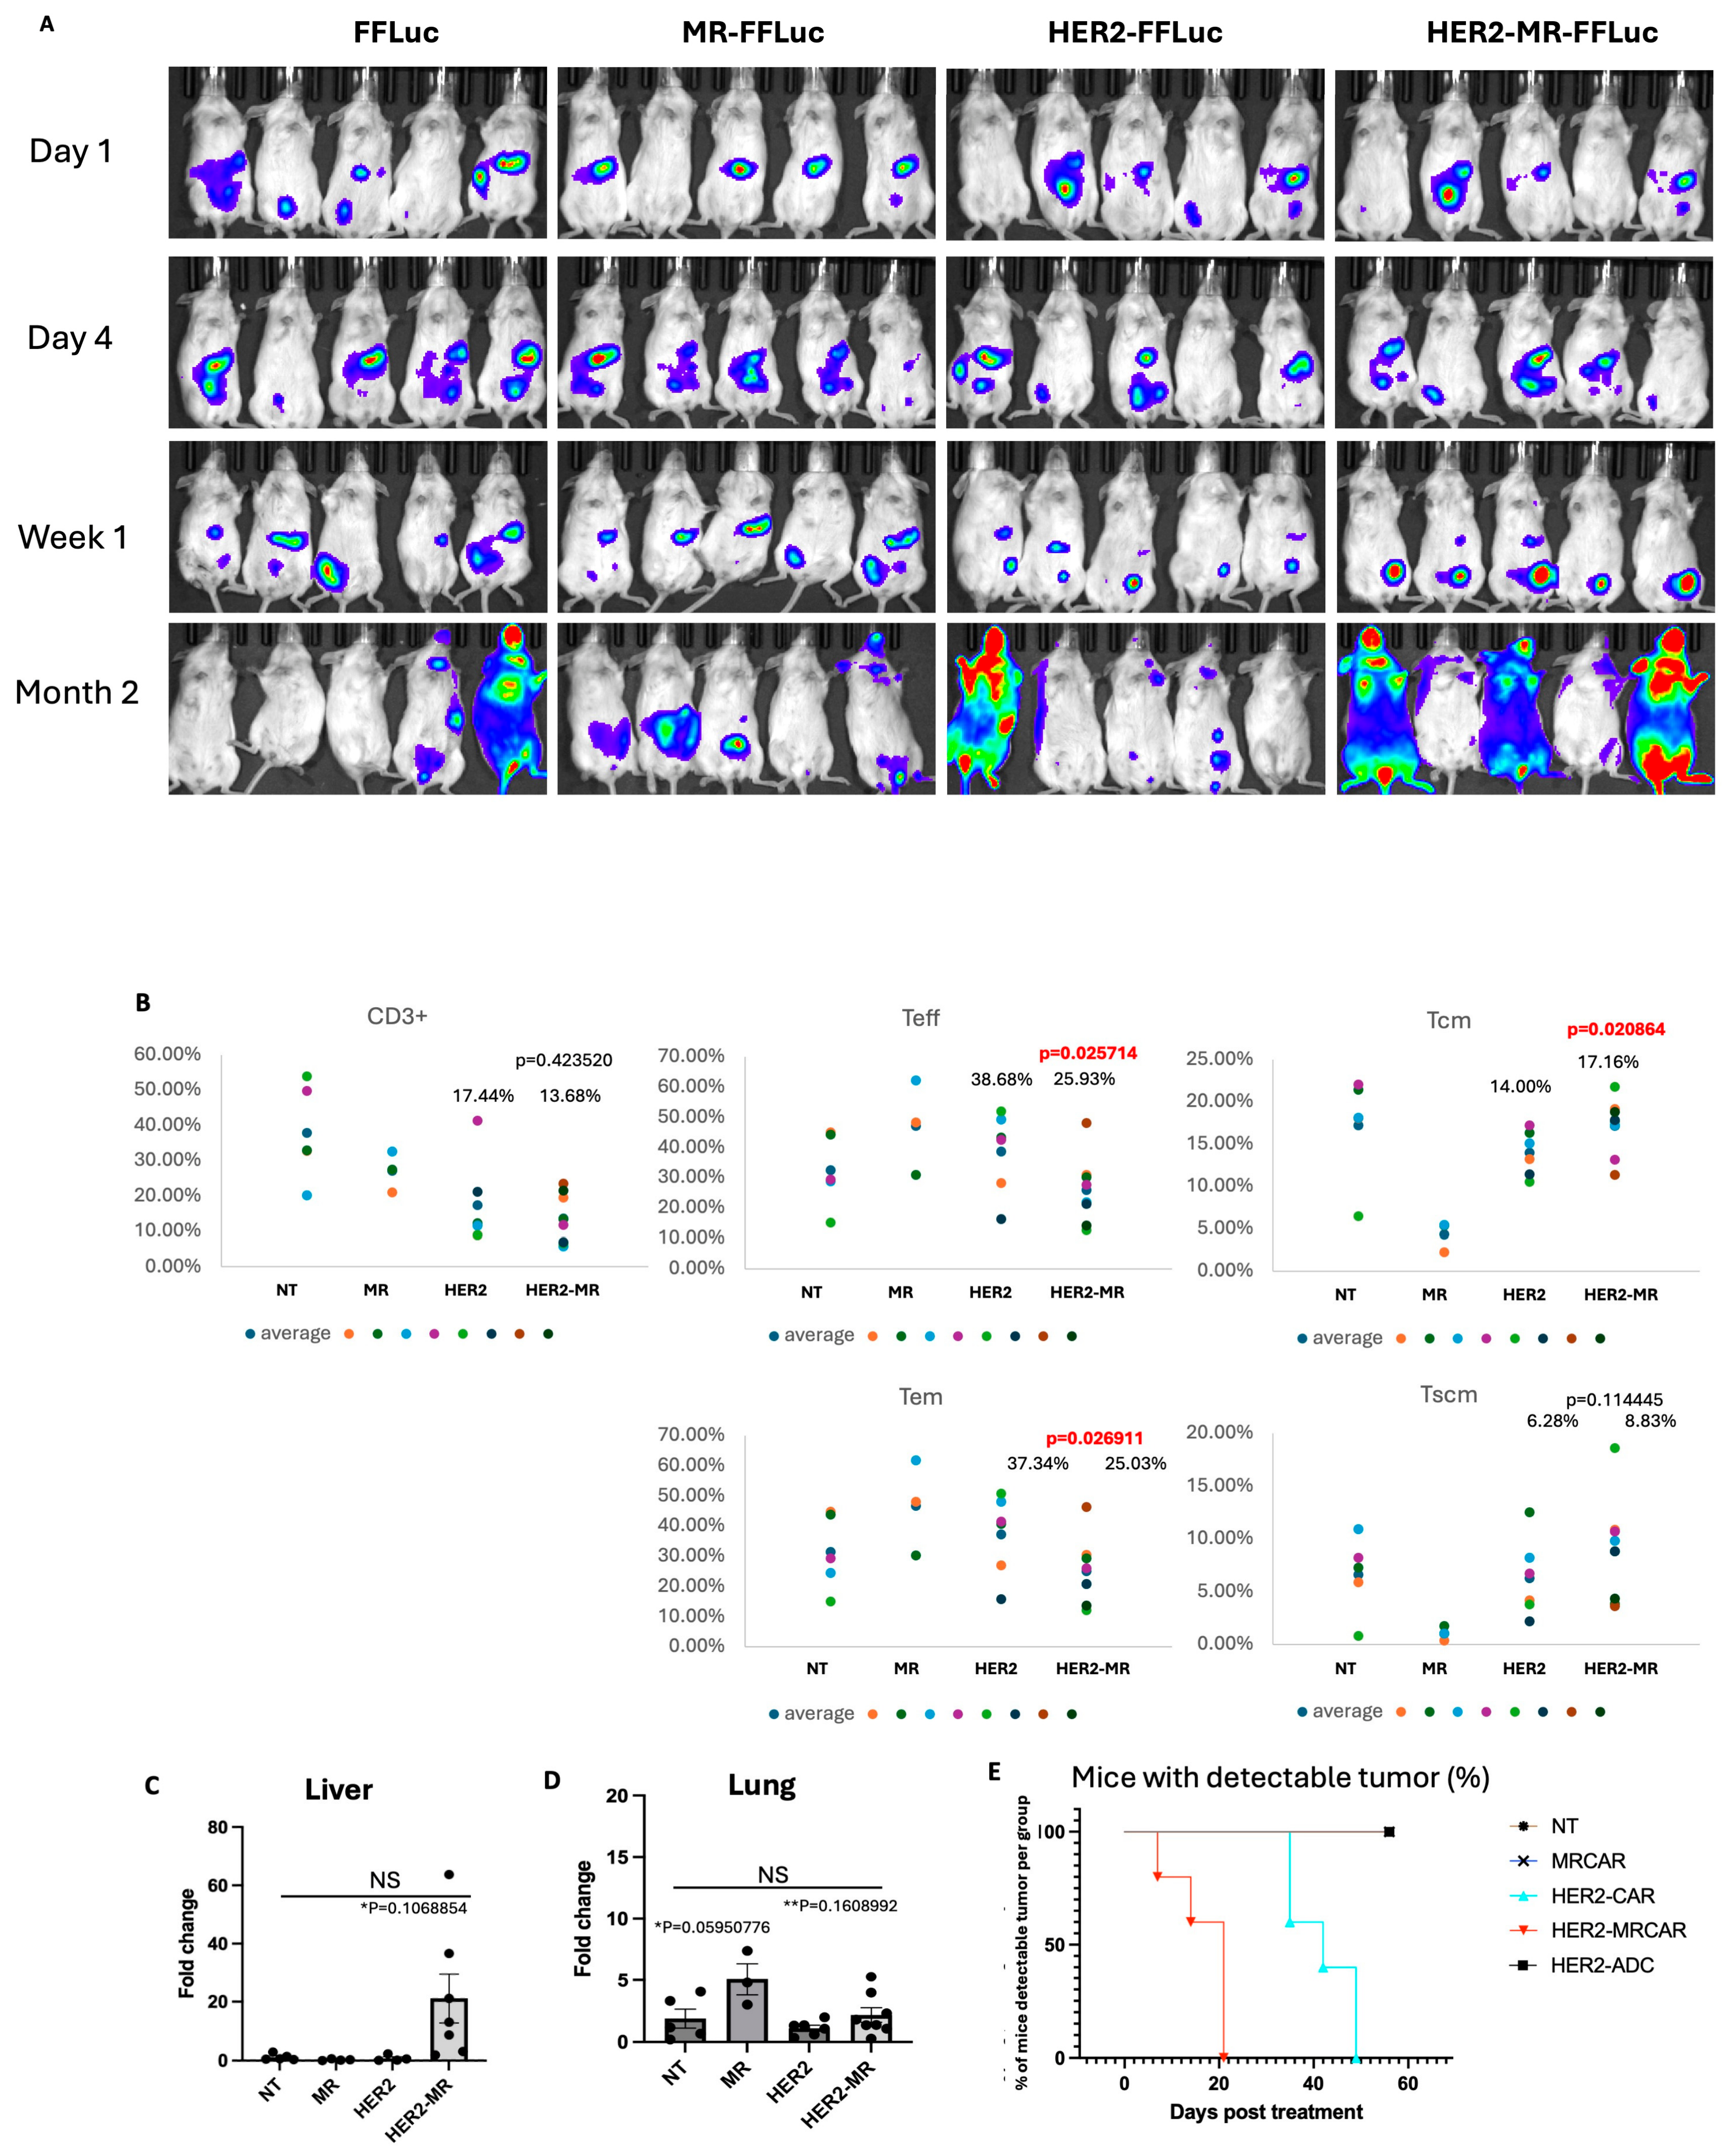
CAR T cell persistence was subsequently monitored by IVIS following infusion into T47D breast cancer xenografts. HER2-MR-FFLuc CAR T cells showed greater accumulation at tumor sites at both early and late time points compared with conventional CAR T cells. Quantitative analysis demonstrated significantly higher photon flux in the MRCAR group (p<0.01, n=5, Fig. 5A). Phenotypic analysis further revealed increased proportions of central memory (Tcm) and stem memory (Tscm) populations in MRCAR T cells (Fig. 5B), suggesting enhanced capacity for long-term persistence and recall responses. CAR T-cell distribution in the liver and lung was further assessed by qPCR, with no significant differences in CAR T-cell abundance among the groups (Fig. 5C-D).
Consistent with these findings, MRCAR treatment produced earlier and more sustained tumor control in the primary therapeutic model. Tumor-free status was achieved by approximately day 21 in the HER2-MRCAR group compared with day 49 in the HER2-CAR group, whereas tumors continued to grow in the HER2-ADC-treated group through day 54 (p<0.01, Fig. 5E). Collectively, these results indicate that ADA1–CD26 rewiring promotes CAR T cell persistence and memory-associated phenotypes, supporting durable antitumor activity in breast cancer models.
ADA1–CD26 Axis Attenuates Systemic Toxicity and Modulates Macrophage Polarization
To determine whether incorporation of ADA1 and CD26 could mitigate inflammatory toxicity while preserving antitumor efficacy, NSG mice bearing intraperitoneal (i.p.) luciferase-expressing Huh7 tumors were treated with either MRCAR or conventional CAR T cells (n = 5 female and 5 male mice per group). All GPC3-targeted CAR T-cell treatment groups achieved complete tumor clearance by one week after treatment, as evidenced by in vivo bioluminescence imaging. Despite this comparable antitumor response, mice treated with IL15-GPC3-CAR T cells exhibited substantial mortality, with survival declining in a pattern similar to that observed in untreated tumor-bearing mice in both female and male cohorts. In contrast, treatment with IL15-GPC3-MRCAR T cells significantly improved survival in both female and male mice compared with conventional IL15-GPC3-CAR T cells (log-rank p < 0.01; Fig. 6A–C). These findings suggest that incorporation of ADA1 and CD26 substantially improves the safety profile of IL15-armed GPC3-CAR T cells without compromising their antitumor efficacy.
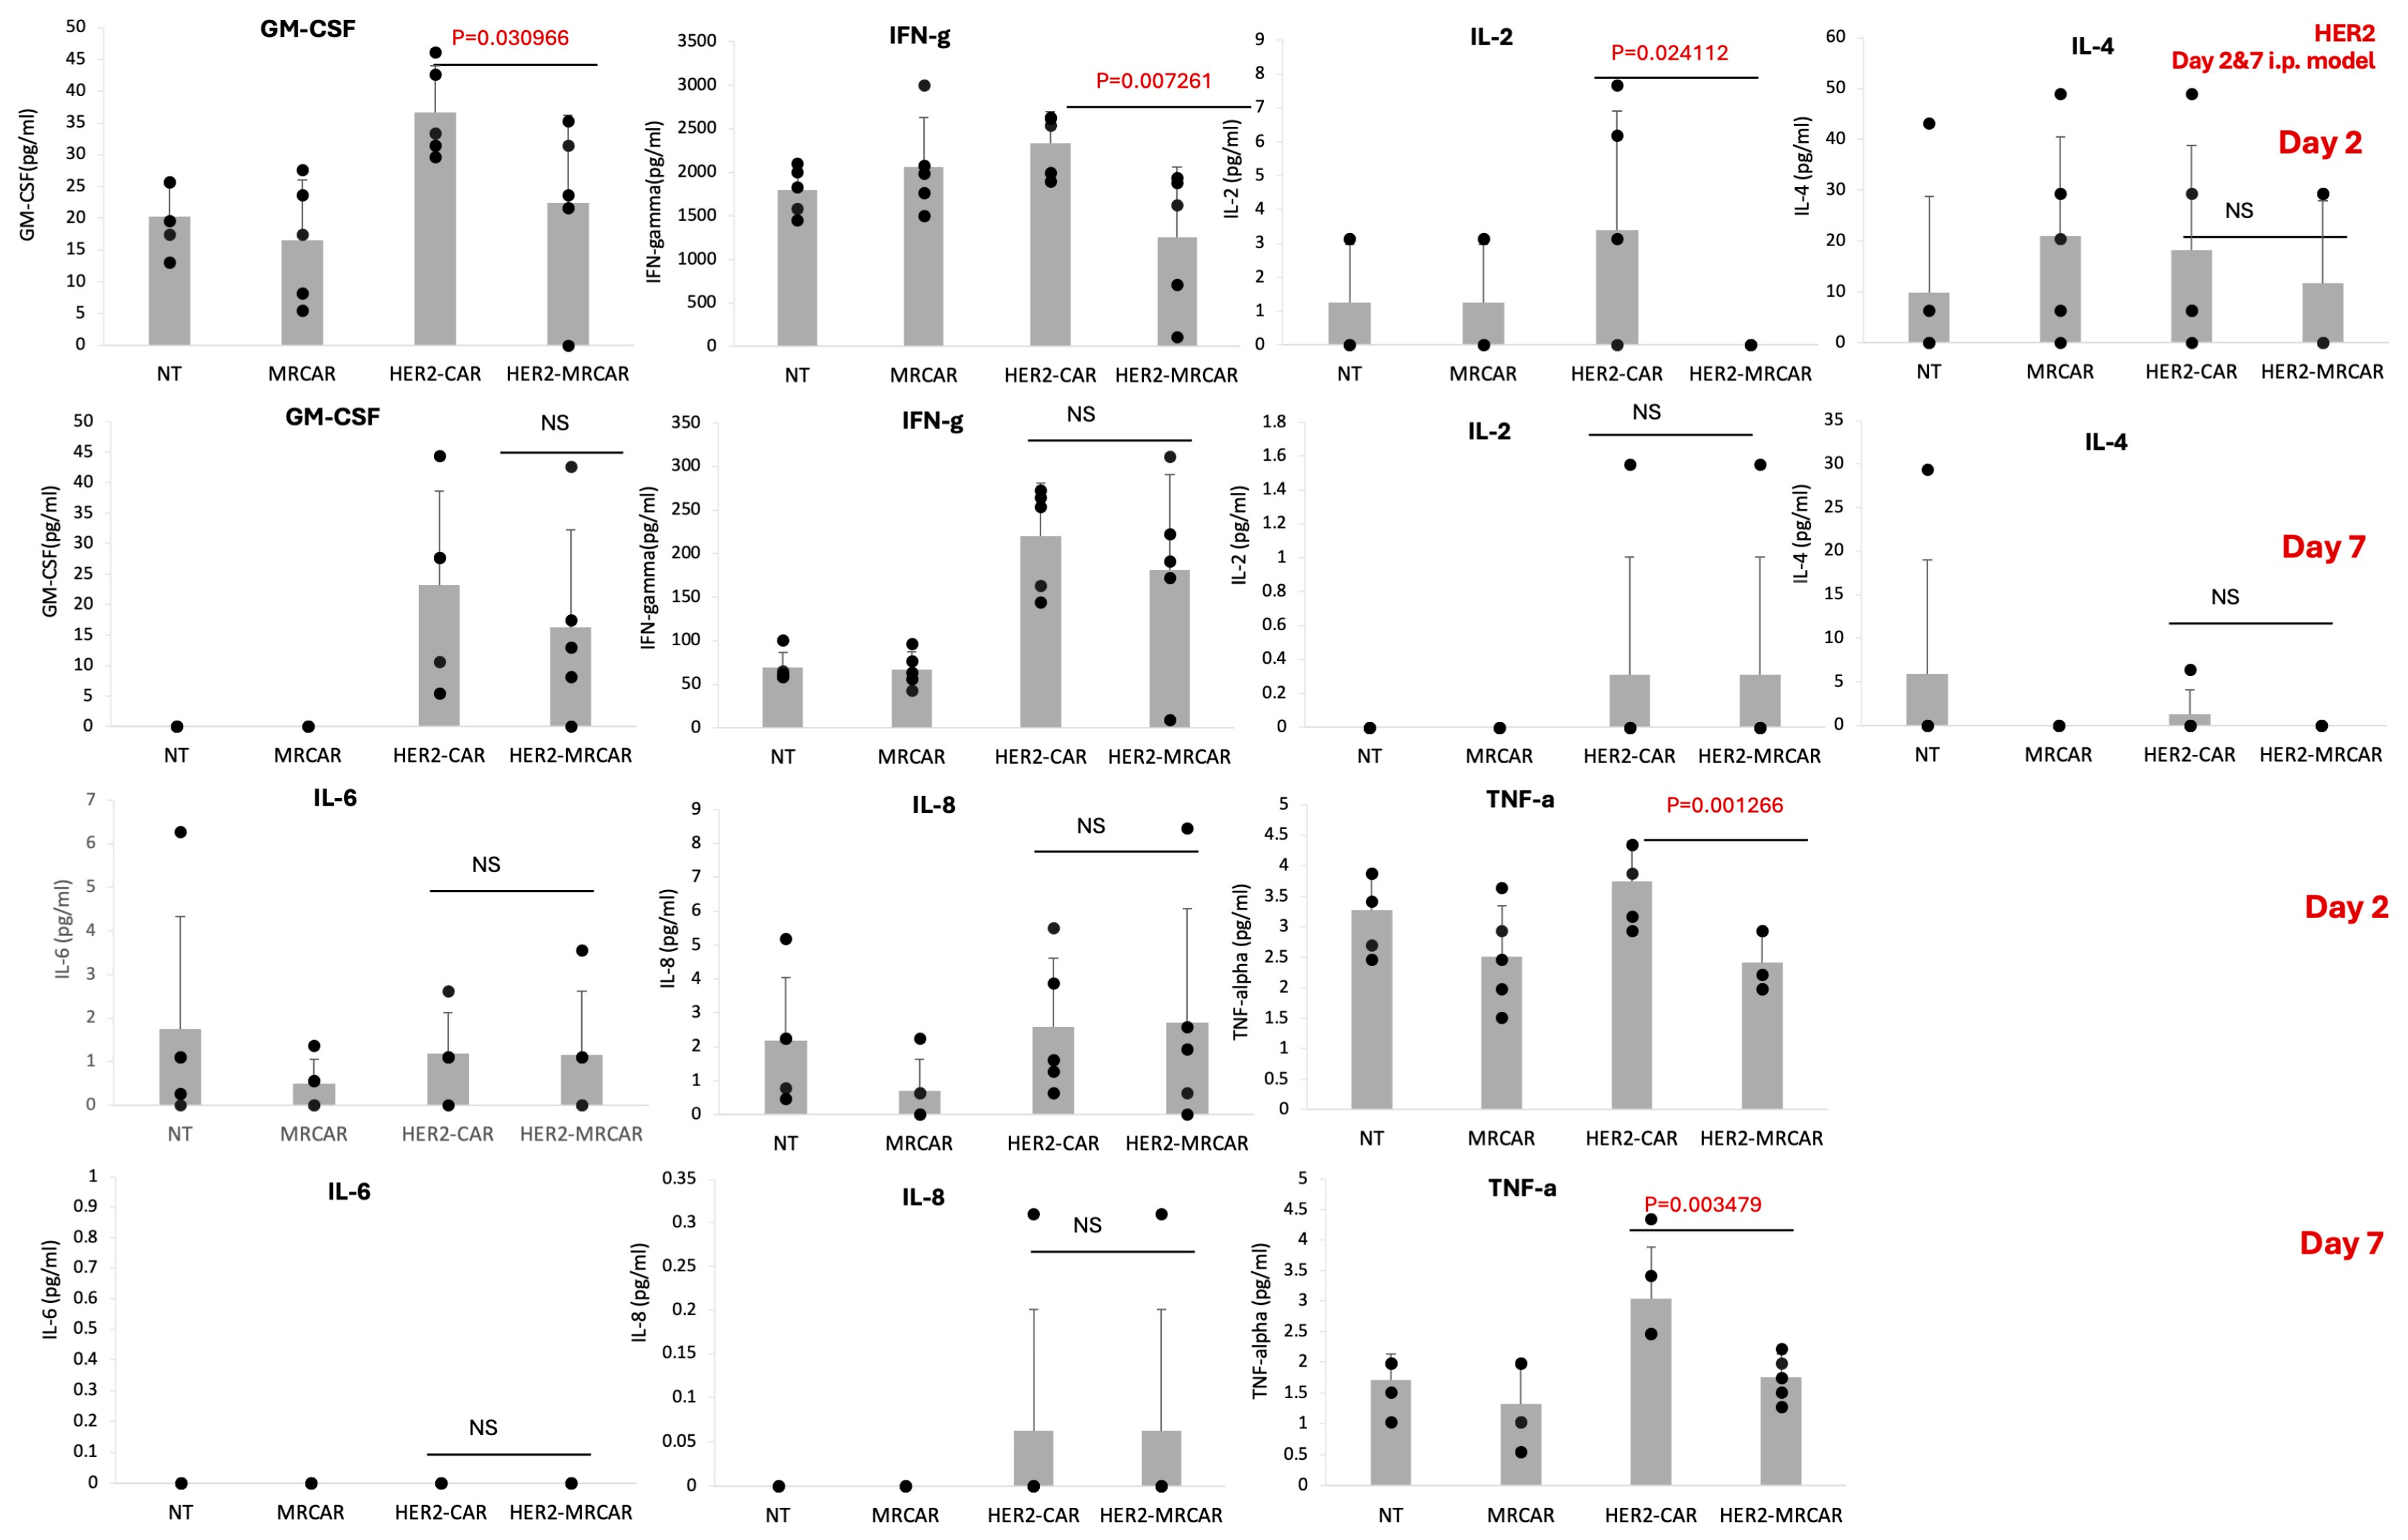
Multiplex cytokine analysis further demonstrated that MRCAR treatment attenuated systemic inflammatory responses following CAR T-cell administration. In the i.p. Huh7 model, serum cytokine profiling at days 2 and 7 revealed distinct inflammatory responses between conventional IL15-GPC3-CAR and IL15-GPC3-MRCAR T-cell treatments. At day 2, serum IFN-γ and IL-4 levels were significantly elevated following IL15-GPC3-CAR T-cell treatment, whereas these increases were not observed in the MRCAR-treated group. By day 7, TNF-α and MCP-1 were similarly increased in mice treated with IL15-GPC3-CAR T cells but remained comparatively low following MRCAR treatment (p < 0.001, n = 3–5 per time point; Fig. 6D). A similar pattern of reduced systemic cytokine production following MRCAR treatment was observed in the HER2-targeted CAR T-cell i.p. model at both days 2 and 7 (sFig. 2).
Figure 6.
ADA1–CD26 mitigates cytokine release syndrome and improves survival in HCC model. To establish a systemic toxicity model, NSG mice were engrafted intraperitoneally (i.p.) with 2 × 10⁶ Huh7 tumor cells, followed by i.p. administration of 1 × 10⁷ CAR T cells together with 1 × 10⁷ PBMCs. (A–C) Kaplan–Meier survival curves of female and male NSG mice bearing Huh7 tumors following CAR T-cell treatment. (D–E) Serum cytokine levels measured in peripheral blood collected on days 2 and 7 after CAR T-cell administration. (F–H) In vitro macrophage co-culture: quantification of M1-like (F) and M2-like (G) polarization and cytokine profile after exposure to IL15-GPC3-CAR or MRCAR T cells. (H) T cell expansion in macrophage/T cell cocultures with GPC3-Huh7 targets, showing enhanced proliferation and viability in the MRCAR group (mean ± SEM, n=3). Statistical analysis as indicated in figure; p < 0.05.
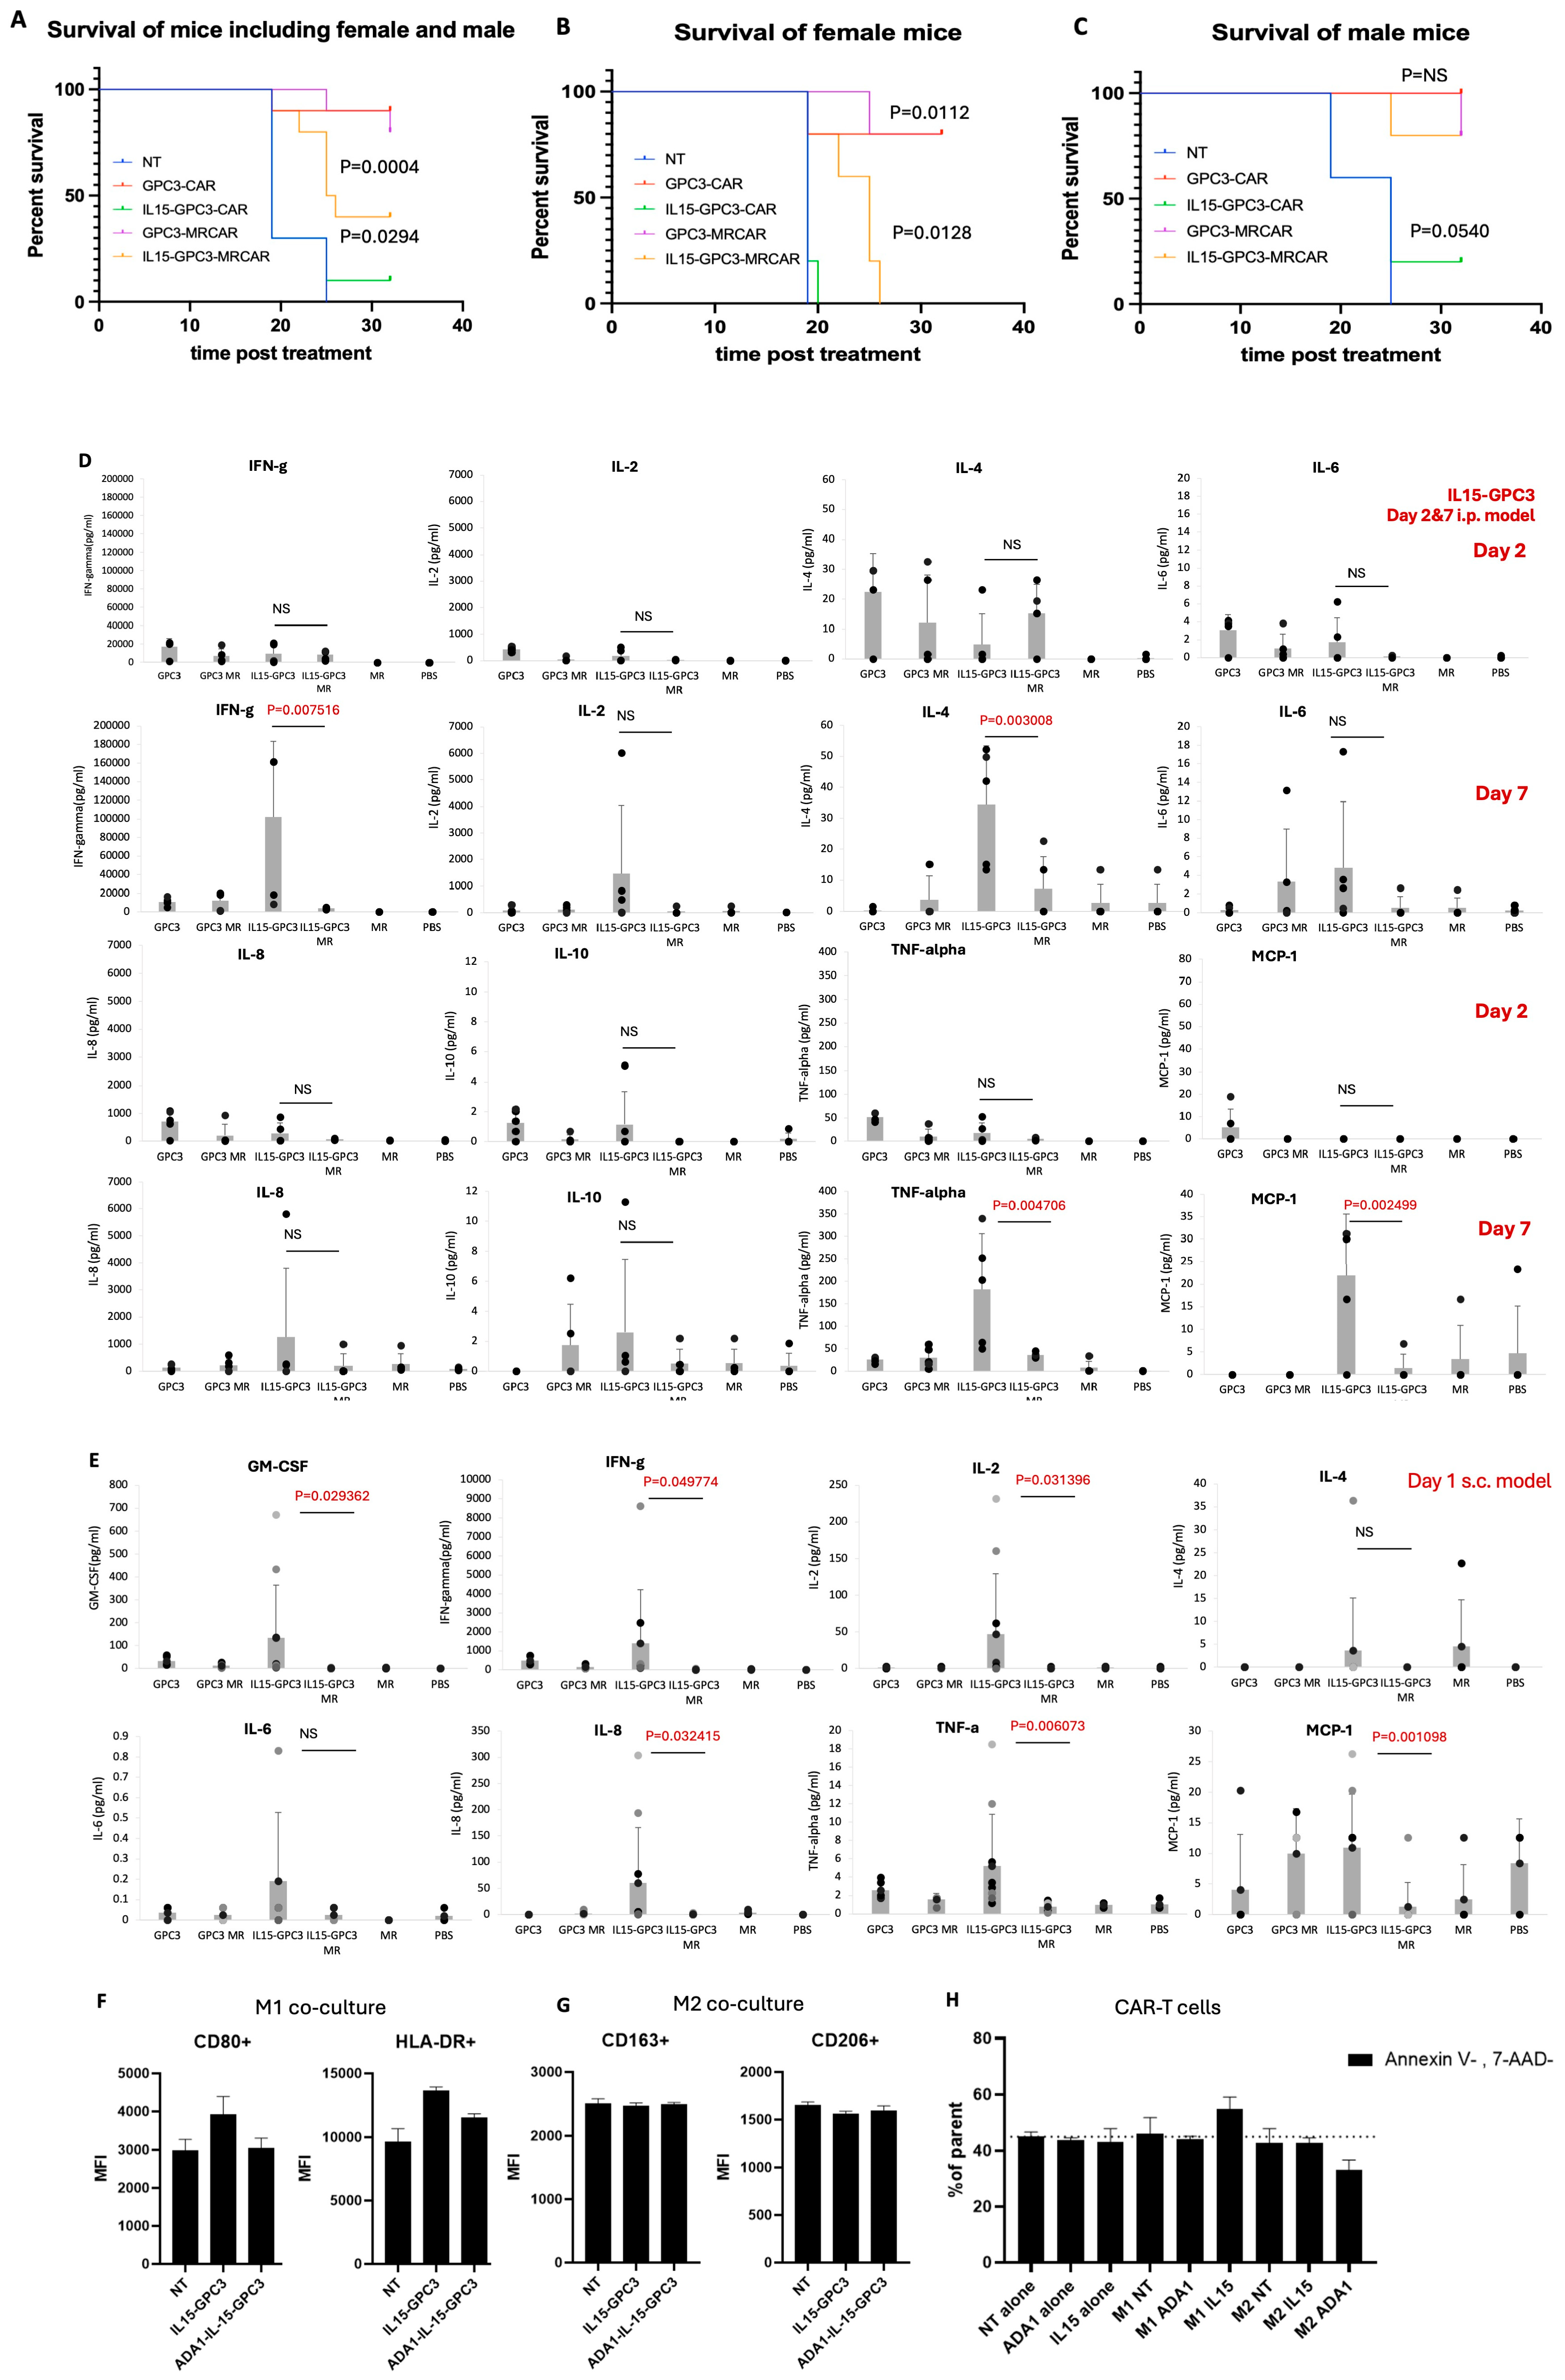
Consistent with these findings, in the s.c. Huh7 model, serum levels of GM-CSF, IFN-γ, IL-2, IL-8, TNF-α, and MCP-1 were significantly elevated one day after administration of IL15-GPC3-CAR T cells compared with untreated mice, whereas these cytokines were not significantly increased following IL15-GPC3-MRCAR treatment (Fig. 6E). Because CAR T cells administered systemically in the s.c. model are unlikely to have substantially encountered the tumor within this early time window, the acute cytokine response may, at least in part, reflect antigen-independent or nonspecific immune activation associated with IL15-armed CAR T cells rather than tumor-directed activity. Collectively, these findings suggest that conventional IL15-CAR T cells can induce excessive systemic cytokine activation, whereas incorporation of ADA1 and CD26 substantially attenuates this response, potentially contributing to the improved safety and survival observed with MRCAR treatment.
Because macrophages can substantially influence inflammation and T-cell function within the tumor microenvironment, macrophage co-culture experiments were performed to further investigate the immunomodulatory effects of MRCAR T cells. Conventional IL15-expressing CAR T cells induced macrophage activation, as evidenced by increased expression of the M1-associated markers CD80 and HLA-DR, whereas IL15-MRCAR T cells markedly attenuated this inflammatory response (p < 0.01, n = 3; Fig. 6F–H). Notably, conventional IL15-CAR T cells also exhibited greater expansion in the presence of macrophages, suggesting that this enhanced proliferation may be accompanied by increased macrophage-mediated inflammatory activation. In contrast, MRCAR T cells maintained their therapeutic activity while limiting this proinflammatory macrophage response. Collectively, these findings support a role for ADA1–CD26 rewiring in improving CAR T-cell persistence and antitumor activity while simultaneously attenuating inflammatory activation and promoting a less inflammatory tumor immune microenvironment.
Scheme 2.
ADA1–CD26 mitigates systemic toxicities in T47D model. NSG mice were engrafted with 1 × 10⁷ T47D tumor cells in the 4th mammary fat pad, followed by i.p. administration of 1 × 10⁷ CAR T cells together with 1 × 10⁷ PBMCs. Serum cytokine levels measured in peripheral blood collected on days 2 and 7 after CAR T-cell administration.
4. Discussion
The persistence, expansion, and safe application of CAR T cell therapies in solid tumors remain among the greatest unmet challenges in cancer immunotherapy. Our study demonstrates that metabolic rewiring of CAR T cells via ADA1 and CD26 co-expression, coupled with IL-15 support, profoundly augments their antitumor capabilities while substantially reducing cytokine release syndrome. This multi-receptor CAR approach addresses several key limitations encountered in solid tumor settings, including poor T cell infiltration, rapid exhaustion, limited memory formation, and inflammatory toxicity.
Through systematic in vitro and in vivo characterization, we show that ADA1–CD26 multiplexing enhances the expansion, cytotoxicity, and survival of CAR T cells in models of hepatocellular carcinoma and breast cancer. ADA1 overexpression enabled T cells to metabolize adenosine, a prevalent immunosuppressive metabolite in the tumor microenvironment, thereby restoring metabolic fitness and supporting sustained effector function. This aligns with previous studies implicating adenosine metabolism as a regulatory mechanism for immune cell suppression and highlights ADA1 as a practical target for engineering metabolically resilient T cells (14, 15, 25, 26). The supplementary expression of CD26 further boosted T cell invasiveness, facilitating migration through Matrigel barriers and improving homing to tumor sites via MAPK and PI3K signaling pathways. These results build upon prior work identifying CD26high T subsets as critical for tissue infiltration and functional persistence (14, 15, 28).
Repeated antigen exposure and chronic stimulation are known to induce exhaustion markers and impair CAR T cell efficacy. Here, ADA1–CD26 MRCAR T cells demonstrated marked resistance to exhaustion, maintaining viability and low levels of inhibitory receptor expression after repeated tumor stimulations. The improved expansion and maintenance of memory subsets—including central memory (Tcm) and stem memory (Tscm) populations—provide mechanistic insight into the observed protection against tumor rechallenge in both HCC and breast cancer models. These findings further support the concept that metabolic rewiring promotes a less differentiated phenotype, helping maintain a pool of functional, long-lasting T cells (10, 13, 45-52).
Importantly, our data indicate that ADA1–CD26 rewiring mitigates the risk of systemic toxicity without compromising therapeutic efficacy. ADA1–CD26 MRCAR T cells produced significantly lower levels of pro-inflammatory cytokines (IL-6, IFN-γ, TNF-α) in vivo and induced changes in macrophage polarization favoring M1-like over M2-like phenotypes, thereby contributing to a more favorable immune profile. This dual effect—improved antitumor response and reduced systemic toxicity—addresses a major safety concern and is likely attributable to both metabolic normalization and immune reprogramming of the tumor microenvironment. Recent clinical experience with IL-15–enhanced CAR T therapies has underscored the risk of hyperinflammation (20), yet our data show that ADA1–CD26 can provide a safety brake even alongside potent expansion signal.
The translational implications of our findings are significant. By combining metabolic, migratory, and survival enhancements, ADA1–CD26-based CAR T cells may overcome major bottlenecks hampering solid tumor immunotherapy, potentially increasing response rates and treatment durability, while minimizing toxicity. In particular, the sustained efficacy and rechallenge protection observed here support the development of “off-the-shelf” or repeated dosing strategies. This platform may be adapted to multiple antigen targets across cancer types, as illustrated by performance in both GPC3-positive HCC and HER2-positive breast cancer.
Despite these promising results, several limitations warrant further investigation. First, although our murine models recapitulate key aspects of human solid tumors, differences in the human immune response and tumor architecture may influence clinical translation. Second, long-term follow-up studies are needed to determine whether metabolic rewiring affects T cell persistence and function beyond the timeframes studied here. Third, the potential for off-target effects or metabolic imbalances must be evaluated by tracking ADA1 and CD26 expression in non-tumor tissues, as well as monitoring for secondary toxicity. Finally, future work should explore combinatorial approaches involving checkpoint blockade or novel CAR designs to optimize the metabolic and immune landscape.
In conclusion, our study establishes ADA1–CD26 metabolic rewiring as a potent strategy for next-generation CAR T cell therapies in solid tumors, promoting tumor infiltration, persistence, and immune safety. These results provide a robust foundation for clinical development and lay the groundwork for overcoming longstanding barriers in solid tumor immunotherapy.
Author Contributions
Conceptualization, X.S., S.G., and A.H.; methodology, Y.H and X.S., formal analysis, Y.H., K.S. and X.S.; data generation, Y.H. and X.S.; writing and editing, K.S. and X.S.; supervision, X.S.; funding, X.S. All authors have read and agreed to the published version of the manuscript.
Funding
This study was supported by DOD Lung Cancer Research Program Idea Award W81XWH2210701, and Department of DOD Breast Cancer Research Program Translation Award HT9425-24-1-0031 to XS, and NIH 2R37AI114581, 5R01CA299046, and 5R01AI175004 to RW. This work was also supported in part by Cancer Prevention & Research Institute of Texas Proteomics & Metabolomics Core Facility Support Award (RP210227) and NCI Cancer Center Support Grant (P30CA125123) to the Antibody-based Proteomics Core/Shared Resource (SH) at Texas A&M University.
Acknowledgments
We thank Michael Nguyen and Yuan Yao for their excellent technical support with Luminex assays at the Antibody-based Proteomics Core/Shared Resource. We also thank Didem Cobanoglu for technical support with macrophage experiments. A large language model (OpenAI’s ChatGPT) was used for language editing during the preparation of this manuscript. The authors reviewed and edited the final version.
Conflicts of Interest
XS is the founder of Cellula BioPharma, Inc., which holds a licensing agreement with Texas A&M University related to technology described in this article. XS, RW, and YH are co-inventors of this related technology. SG is a co-inventor on patent applications and patents in the fields of cell and gene therapy for cancer. During the past two years, he has served as a member of the Data and Safety Monitoring Board of Immatics and on the Scientific Advisory Boards of Be Biopharma and Tikva Allocell. The other authors declare no competing interests.
References
- Lee DW, Kochenderfer JN, Stetler-Stevenson M, Cui YK, Delbrook C, Feldman SA, et al. T cells expressing CD19 chimeric antigen receptors for acute lymphoblastic leukaemia in children and young adults: a phase 1 dose-escalation trial. Lancet. 2015;385(9967):517–28. Epub 20141013. PubMed PMID: 25319501; PubMed Central PMCID: PMC7065359. [CrossRef]
- Turtle CJ, Hanafi LA, Berger C, Gooley TA, Cherian S, Hudecek M, et al. CD19 CAR-T cells of defined CD4+:CD8+ composition in adult B cell ALL patients. J Clin Invest. 2016;126(6):2123–38. Epub 20160425. PubMed PMID: 27111235; PubMed Central PMCID: PMC4887159. [CrossRef]
- Turtle CJ, Hanafi LA, Berger C, Hudecek M, Pender B, Robinson E, et al. Immunotherapy of non-Hodgkin’s lymphoma with a defined ratio of CD8+ and CD4+ CD19-specific chimeric antigen receptor-modified T cells. Sci Transl Med. 2016;8(355):355ra116. PubMed PMID: 27605551; PubMed Central PMCID: PMC5045301. [CrossRef]
- Liang Y, Liu H, Lu Z, Lei W, Zhang C, Li P, et al. CD19 CAR-T expressing PD-1/CD28 chimeric switch receptor as a salvage therapy for DLBCL patients treated with different CD19-directed CAR T-cell therapies. J Hematol Oncol. 2021;14(1):26. Epub 20210216. PubMed PMID: 33593414; PubMed Central PMCID: PMC7885572. [CrossRef]
- Liu H, Lei W, Zhang C, Yang C, Wei J, Guo Q, et al. CD19-specific CAR T Cells that Express a PD-1/CD28 Chimeric Switch-Receptor are Effective in Patients with PD-L1-positive B-Cell Lymphoma. Clin Cancer Res. 2021;27(2):473–84. Epub 20201007. PubMed PMID: 33028589. [CrossRef]
- Jacobson CA, Chavez JC, Sehgal AR, William BM, Munoz J, Salles G, et al. Axicabtagene ciloleucel in relapsed or refractory indolent non-Hodgkin lymphoma (ZUMA-5): a single-arm, multicentre, phase 2 trial. Lancet Oncol. 2022;23(1):91–103. Epub 20211208. PubMed PMID: 34895487. [CrossRef]
- Davila ML, Riviere I, Wang X, Bartido S, Park J, Curran K, et al. Efficacy and toxicity management of 19-28z CAR T cell therapy in B cell acute lymphoblastic leukemia. Sci Transl Med. 2014;6(224):224ra25. PubMed PMID: 24553386; PubMed Central PMCID: PMC4684949. [CrossRef]
- Majzner RG, Mackall CL. Tumor Antigen Escape from CAR T-cell Therapy. Cancer Discov. 2018;8(10):1219–26. Epub 20180822. PubMed PMID: 30135176. [CrossRef]
- Lemoine J, Ruella M, Houot R. Born to survive: how cancer cells resist CAR T cell therapy. J Hematol Oncol. 2021;14(1):199. Epub 20211122. PubMed PMID: 34809678; PubMed Central PMCID: PMC8609883. [CrossRef]
- Hu X, Chao M, Wu H. Central role of lactate and proton in cancer cell resistance to glucose deprivation and its clinical translation. Signal Transduct Target Ther. 2017;2:16047. Epub 20170310. PubMed PMID: 29263910; PubMed Central PMCID: PMC5661620. [CrossRef]
- Xu X, Gnanaprakasam JNR, Sherman J, Wang R. A Metabolism Toolbox for CAR T Therapy. Front Oncol. 2019;9:322. Epub 20190430. PubMed PMID: 31114756; PubMed Central PMCID: PMC6503740. [CrossRef]
- Wang T, Gnanaprakasam JNR, Chen X, Kang S, Xu X, Sun H, et al. Inosine is an alternative carbon source for CD8+-T-cell function under glucose restriction. Nat Metab. 2020;2(7):635–47. Epub 20200615. PubMed PMID: 32694789; PubMed Central PMCID: PMC7371628. [CrossRef]
- Vander Heiden MG, Cantley LC, Thompson CB. Understanding the Warburg effect: the metabolic requirements of cell proliferation. Science. 2009;324(5930):1029–33. PubMed PMID: 19460998; PubMed Central PMCID: PMC2849637. [CrossRef]
- Hu Y, Sarkar A, Song K, Michael S, Hook M, Wang R, et al. Selective refueling of CAR T cells using ADA1 and CD26 boosts antitumor immunity. Cell Rep Med. 2024;5(5):101530. Epub 20240429. PubMed PMID: 38688275; PubMed Central PMCID: PMC11148642. [CrossRef]
- Hu Y, Sarkar A, Song X. Protocol for preparing metabolically reprogrammed human CAR T cells and evaluating their in vitro effects. STAR Protoc. 2024;5(4):103333. Epub 20240921. PubMed PMID: 39306853; PubMed Central PMCID: PMC11447407. [CrossRef]
- Song AW, Song X. ADA1-Driven Metabolic Refueling Enhances CAR T Cell Therapy for Solid Tumors. Cancers (Basel). 2025;18(1). Epub 20251222. PubMed PMID: 41514547; PubMed Central PMCID: PMC12784833. [CrossRef]
- Song AW, Song X. Rewiring T Cell Metabolism to Enhance CAR T Cell Function in Solid Tumor Microenvironments. Pharmaceutics. 2025;17(12). Epub 20251126. PubMed PMID: 41471036; PubMed Central PMCID: PMC12735850. [CrossRef]
- Agac Cobanoglu D, Franklin S, Hu Y, Boland DJ, Song X. CAR Intrinsic Design Pre-Shapes Transcriptional and Metabolic Networks in CAR T Cells. Metabolites. 2026;16(1). Epub 20260107. PubMed PMID: 41590660; PubMed Central PMCID: PMC12844403. [CrossRef]
- Batra SA, Rathi P, Guo L, Courtney AN, Fleurence J, Balzeau J, et al. Glypican-3-Specific CAR T Cells Coexpressing IL15 and IL21 Have Superior Expansion and Antitumor Activity against Hepatocellular Carcinoma. Cancer Immunol Res. 2020;8(3):309–20. Epub 20200117. PubMed PMID: 31953246; PubMed Central PMCID: PMC10765595. [CrossRef]
- Steffin D, Ghatwai N, Montalbano A, Rathi P, Courtney AN, Arnett AB, et al. Interleukin-15-armoured GPC3 CAR T cells for patients with solid cancers. Nature. 2025;637(8047):940–6. Epub 20241127. PubMed PMID: 39604730; PubMed Central PMCID: PMC12704925. [CrossRef]
- Gao ZW, Yang L, Liu C, Wang X, Guo WT, Zhang HZ, et al. Distinct Roles of Adenosine Deaminase Isoenzymes ADA1 and ADA2: A Pan-Cancer Analysis. Front Immunol. 2022;13:903461. Epub 20220518. PubMed PMID: 35663977; PubMed Central PMCID: PMC9157497. [CrossRef]
- Gakis C. Adenosine deaminase (ADA) isoenzymes ADA1 and ADA2: diagnostic and biological role. Eur Respir J. 1996;9(4):632–3. PubMed PMID: 8726922. [CrossRef]
- Aghaei M, Karami-Tehrani F, Salami S, Atri M. Adenosine deaminase activity in the serum and malignant tumors of breast cancer: the assessment of isoenzyme ADA1 and ADA2 activities. Clin Biochem. 2005;38(10):887–91. PubMed PMID: 16054616. [CrossRef]
- Zhulai G, Oleinik E, Shibaev M, Ignatev K. Adenosine-Metabolizing Enzymes, Adenosine Kinase and Adenosine Deaminase, in Cancer. Biomolecules. 2022;12(3). Epub 20220308. PubMed PMID: 35327609; PubMed Central PMCID: PMC8946555. [CrossRef]
- Qu Y, Dunn ZS, Chen X, MacMullan M, Cinay G, Wang HY, et al. Adenosine Deaminase 1 Overexpression Enhances the Antitumor Efficacy of Chimeric Antigen Receptor-Engineered T Cells. Hum Gene Ther. 2022;33(5-6):223–36. Epub 20210825. PubMed PMID: 34225478; PubMed Central PMCID: PMC9206478. [CrossRef]
- Renauer P, Park JJ, Bai M, Acosta A, Lee WH, Lin GH, et al. Immunogenetic metabolomics revealed key enzymes that modulate CAR-T metabolism and function. bioRxiv. 2023. Epub 20230315. PubMed PMID: 36993638; PubMed Central PMCID: PMC10055032. [CrossRef]
- Klysz DD, Fowler C, Malipatlolla M, Stuani L, Freitas KA, Chen Y, et al. Inosine induces stemness features in CAR-T cells and enhances potency. Cancer Cell. 2024;42(2):266–82.e8. Epub 20240125. PubMed PMID: 38278150. [CrossRef]
- Bailey SR, Nelson MH, Majchrzak K, Bowers JS, Wyatt MM, Smith AS, et al. Human CD26high T cells elicit tumor immunity against multiple malignancies via enhanced migration and persistence. Nat Commun. 2017;8(1):1961. Epub 20171206. PubMed PMID: 29213079; PubMed Central PMCID: PMC5719008. [CrossRef]
- Li W, Guo L, Rathi P, Marinova E, Gao X, Wu MF, et al. Redirecting T Cells to Glypican-3 with 4-1BB Zeta Chimeric Antigen Receptors Results in Th1 Polarization and Potent Antitumor Activity. Hum Gene Ther. 2017;28(5):437–48. Epub 20160816. PubMed PMID: 27530312; PubMed Central PMCID: PMC5444493. [CrossRef]
- Ahmed N, Brawley VS, Hegde M, Robertson C, Ghazi A, Gerken C, et al. Human Epidermal Growth Factor Receptor 2 (HER2) -Specific Chimeric Antigen Receptor-Modified T Cells for the Immunotherapy of HER2-Positive Sarcoma. J Clin Oncol. 2015;33(15):1688–96. Epub 20150323. PubMed PMID: 25800760; PubMed Central PMCID: PMC4429176. [CrossRef]
- Ahmed N, Brawley V, Hegde M, Bielamowicz K, Kalra M, Landi D, et al. HER2-Specific Chimeric Antigen Receptor-Modified Virus-Specific T Cells for Progressive Glioblastoma: A Phase 1 Dose-Escalation Trial. JAMA Oncol. 2017;3(8):1094–101. PubMed PMID: 28426845; PubMed Central PMCID: PMC5747970. [CrossRef]
- Zhuang H, Cao G, Kou C, Liu T. CCL2/CCR2 axis induces hepatocellular carcinoma invasion and epithelial-mesenchymal transition in vitro through activation of the Hedgehog pathway. Oncol Rep. 2018;39(1):21–30. Epub 20171102. PubMed PMID: 29115520; PubMed Central PMCID: PMC5783597. [CrossRef]
- Gu M, Wang X. Pseudogene MSTO2P Interacts with miR-128-3p to Regulate Coptisine Sensitivity of Non-Small-Cell Lung Cancer (NSCLC) through TGF-. J Oncol. 2022;2022:9864411. Epub 20220626. PubMed PMID: 35794983; PubMed Central PMCID: PMC9251142. [CrossRef]
- Yuan R, Fan Q, Liang X, Han S, He J, Wang QQ, et al. Cucurbitacin B inhibits TGF-β1-induced epithelial-mesenchymal transition (EMT) in NSCLC through regulating ROS and PI3K/Akt/mTOR pathways. Chin Med. 2022;17(1):24. Epub 20220219. PubMed PMID: 35183200; PubMed Central PMCID: PMC8858510. [CrossRef]
- Havre PA, Abe M, Urasaki Y, Ohnuma K, Morimoto C, Dang NH. CD26 expression on T cell lines increases SDF-1-alpha-mediated invasion. Br J Cancer. 2009;101(6):983–91. Epub 20090804. PubMed PMID: 19654580; PubMed Central PMCID: PMC2743358. [CrossRef]
- Xie J, Wang W, Si JW, Miao XY, Li JC, Wang YC, et al. Notch signaling regulates CXCR4 expression and the migration of mesenchymal stem cells. Cell Immunol. 2013;281(1):68–75. Epub 20130213. PubMed PMID: 23474530. [CrossRef]
- Mezawa Y, Daigo Y, Takano A, Miyagi Y, Yokose T, Yamashita T, et al. CD26 expression is attenuated by TGF-β and SDF-1 autocrine signaling on stromal myofibroblasts in human breast cancers. Cancer Med. 2019;8(8):3936–48. Epub 20190529. PubMed PMID: 31140748; PubMed Central PMCID: PMC6639198. [CrossRef]
- Corn PG, Zhang M, Nogueras-Gonzalez GM, Xiao L, Zurita AJ, Subudhi SK, et al. A Phase II Study of Cabozantinib and Androgen Ablation in Patients with Hormone-Naïve Metastatic Prostate Cancer. Clin Cancer Res. 2020;26(5):990–9. Epub 20200115. PubMed PMID: 31941830. [CrossRef]
- Msaouel P, Zurita AJ, Huang S, Jonasch E, Tannir NM. Plasma cytokine and angiogenic factors associated with prognosis and therapeutic response to sunitinib vs everolimus in advanced non-clear cell renal cell carcinoma. Oncotarget. 2017;8(26):42149–58. PubMed PMID: 28178674; PubMed Central PMCID: PMC5522056. [CrossRef]
- Egler RA, Li Y, Dang TA, Peters TL, Leung E, Huang S, et al. An integrated proteomic approach to identifying circulating biomarkers in high-risk neuroblastoma and their potential in relapse monitoring. Proteomics Clin Appl. 2011;5(9-10):532–41. Epub 20110907. PubMed PMID: 21833997; PubMed Central PMCID: PMC3685293. [CrossRef]
- Peng SB, Peek V, Zhai Y, Paul DC, Lou Q, Xia X, et al. Akt activation, but not extracellular signal-regulated kinase activation, is required for SDF-1alpha/CXCR4-mediated migration of epitheloid carcinoma cells. Mol Cancer Res. 2005;3(4):227–36. PubMed PMID: 15831676. [CrossRef]
- Chinni SR, Sivalogan S, Dong Z, Filho JC, Deng X, Bonfil RD, et al. CXCL12/CXCR4 signaling activates Akt-1 and MMP-9 expression in prostate cancer cells: the role of bone microenvironment-associated CXCL12. Prostate. 2006;66(1):32–48. PubMed PMID: 16114056. [CrossRef]
- de Goeij BE, Peipp M, de Haij S, van den Brink EN, Kellner C, Riedl T, et al. HER2 monoclonal antibodies that do not interfere with receptor heterodimerization-mediated signaling induce effective internalization and represent valuable components for rational antibody-drug conjugate design. MAbs. 2014;6(2):392–402. Epub 20140103. PubMed PMID: 24492309; PubMed Central PMCID: PMC3984328. [CrossRef]
- Gupta A, Michelini F, Shao H, Yeh C, Drago JZ, Liu D, et al. EGFR-directed antibodies promote HER2 ADC internalization and efficacy. Cell Rep Med. 2024;5(11):101792. Epub 20241021. PubMed PMID: 39437778; PubMed Central PMCID: PMC11604483. [CrossRef]
- Mediavilla-Varela M, Luddy K, Noyes D, Khalil FK, Neuger AM, Soliman H, et al. Antagonism of adenosine A2A receptor expressed by lung adenocarcinoma tumor cells and cancer associated fibroblasts inhibits their growth. Cancer Biol Ther. 2013;14(9):860–8. Epub 20130717. PubMed PMID: 23917542; PubMed Central PMCID: PMC3909555. [CrossRef]
- Wang T, Liu G, Wang R. The Intercellular Metabolic Interplay between Tumor and Immune Cells. Front Immunol. 2014;5:358. Epub 20140728. PubMed PMID: 25120544; PubMed Central PMCID: PMC4112791. [CrossRef]
- Ho PC, Bihuniak JD, Macintyre AN, Staron M, Liu X, Amezquita R, et al. Phosphoenolpyruvate Is a Metabolic Checkpoint of Anti-tumor T Cell Responses. Cell. 2015;162(6):1217–28. Epub 20150827. PubMed PMID: 26321681; PubMed Central PMCID: PMC4567953. [CrossRef]
- Patsoukis N, Bardhan K, Chatterjee P, Sari D, Liu B, Bell LN, et al. PD-1 alters T-cell metabolic reprogramming by inhibiting glycolysis and promoting lipolysis and fatty acid oxidation. Nat Commun. 2015;6:6692. Epub 20150326. PubMed PMID: 25809635; PubMed Central PMCID: PMC4389235. [CrossRef]
- Tkachev V, Goodell S, Opipari AW, Hao LY, Franchi L, Glick GD, et al. Programmed death-1 controls T cell survival by regulating oxidative metabolism. J Immunol. 2015;194(12):5789–800. Epub 20150513. PubMed PMID: 25972478; PubMed Central PMCID: PMC4562423. [CrossRef]
- Chang CH, Qiu J, O’Sullivan D, Buck MD, Noguchi T, Curtis JD, et al. Metabolic Competition in the Tumor Microenvironment Is a Driver of Cancer Progression. Cell. 2015;162(6):1229–41. Epub 20150827. PubMed PMID: 26321679; PubMed Central PMCID: PMC4864363. [CrossRef]
- Hui S, Ghergurovich JM, Morscher RJ, Jang C, Teng X, Lu W, et al. Glucose feeds the TCA cycle via circulating lactate. Nature. 2017;551(7678):115–8. Epub 20171018. PubMed PMID: 29045397; PubMed Central PMCID: PMC5898814. [CrossRef]
- Yadav P, Pandey VK, Shankar BS. Proteomic analysis of radio-resistant breast cancer xenografts: Increased TGF-β signaling and metabolism. Cell Biol Int. 2021;45(4):804–19. Epub 20201231. PubMed PMID: 33325135. [CrossRef]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.