

Submitted:
07 September 2026
Posted:
08 September 2026
Read the latest preprint version here
Abstract
Dissociative Identity Disorder (DID), formerly known as multiple personality disorder, is recognized as one of the most complex conditions in the fields of psychiatry and psychology. Initially associated with interpretations of demonic possession, it later came to be understood from a clinical perspective through the contributions of scholars such as Rush, Charcot, and Janet, who emphasized its dissociative nature. The former diagnostic category of hysteria was subsequently reorganized within modern psychiatric classification systems while preserving its underlying conceptual framework. Furthermore, widely publicized cases, such as The Three Faces of Eve and Sybil, contributed to strengthening the association between DID and early-life trauma. It is estimated that 1.5% of the Brazilian population is affected by DID. Between 2018 and 2023, Brazil's Ministry of Health recorded 3,667 cases. This study was conducted as a narrative, descriptive, and exploratory literature review, drawing on databases including Google Scholar, SciELO, and PePSIC, as well as scientific publications, using specific search descriptors related to dissociation and Dissociative Identity Disorder.
Keywords:
dissociation
; psychoanalysis
; psychopathology
; mental health
; mental disorders
1. Introduction
Dissociative Identity Disorder (DID), formerly referred to as multiple personality disorder, is recognized as one of the most complex clinical conditions in the fields of psychiatry and psychoanalysis. Until the nineteenth century, its manifestations were largely interpreted as demonic possession or other supernatural phenomena. With the advancement of medicine, however, these interpretations were gradually replaced by a clinical perspective, particularly through the contributions of Benjamin Rush, Jean-Martin Charcot, and Pierre Janet, who emphasized the disorder's dissociative nature [1].
The study by Panitz et al.[2] demonstrates that the former diagnostic category of hysteria, described since the time of Hippocrates and extensively investigated by Charcot and Freud, was removed from modern diagnostic classifications and redistributed into categories such as dissociative disorders, somatic symptom and related disorders, depersonalization/derealization disorder, functional neurological symptom disorder, among others. This reclassification did not eliminate the underlying nature of the condition but instead enabled greater diagnostic precision and more accurate clinical investigation. By conceptualizing the fragmentation of consciousness as a response to trauma, Janet anticipated the contemporary understanding of DID, which is currently regarded as an unconscious defensive mechanism against intolerable experiences.
Widely publicized clinical cases, such as those of Chris Costner Sizemore (The Three Faces of Eve) and Shirley Ardell Mason (Sybil), contributed to the popularization of the disorder and reinforced its close association with early traumatic experiences, particularly childhood abuse [1,3,4,5]. Panitz et al. [2] further support this perspective by emphasizing that dissociative disorders are consistently associated with severe trauma, neglect, or abuse, thereby confirming the central role of trauma in the etiology of DID.
From a psychoanalytic perspective, Freud interpreted hysterical symptoms as manifestations of unconscious conflict and sexual repression, whereas Bleuler associated them with schizophrenia. Contemporary authors such as Dell [6] and Maraldi [7] argue that DID should be understood as a complex and chronic dissociative disorder that extends far beyond the mere presence of multiple identities. Panitz et al. [2] further note that although the term hysteria has been abandoned, its conceptual core persists under contemporary diagnostic categories, including DID, dissociative amnesia, and functional neurological symptom disorder.
DID is characterized by the presence of two or more distinct identity states, each with its own memories, behavioral patterns, and even physiological characteristics [1,8]. Furthermore, the disorder is frequently associated with comorbid conditions, including dissociative fugue, psychogenic non-epileptic seizures, and psychosomatic symptoms, highlighting its considerable clinical complexity [9]. By emphasizing unconscious processes and the defensive function of dissociation, psychoanalysis provides a valuable framework for understanding DID as an extreme psychological response to trauma. This fragmentation should not be viewed solely as a pathological phenomenon but also as an unconscious survival strategy, illustrating both the limitations of the human mind when confronted with overwhelming suffering and its remarkable capacity to develop adaptive mechanisms that enable survival.
As a fundamental dimension in the understanding of dissociative disorders, mental health constitutes an essential component of overall quality of life. Rather than merely representing the absence of illness, it encompasses a dynamic state of balance among biological, psychological, social, and cultural factors. This balance is often disrupted by traumatic experiences, neglect, or abuse, making individuals with DID particularly vulnerable. Situating the disorder within this broader framework highlights that its manifestations extend beyond identity fragmentation, reflecting the complex interplay among trauma, subjectivity, and sociocultural context. This perspective underscores the need for integrative and multidisciplinary approaches capable of combining clinical practice with public health policies, thereby promoting not only effective treatment but also conditions that foster the psychological and emotional well-being of affected individuals.
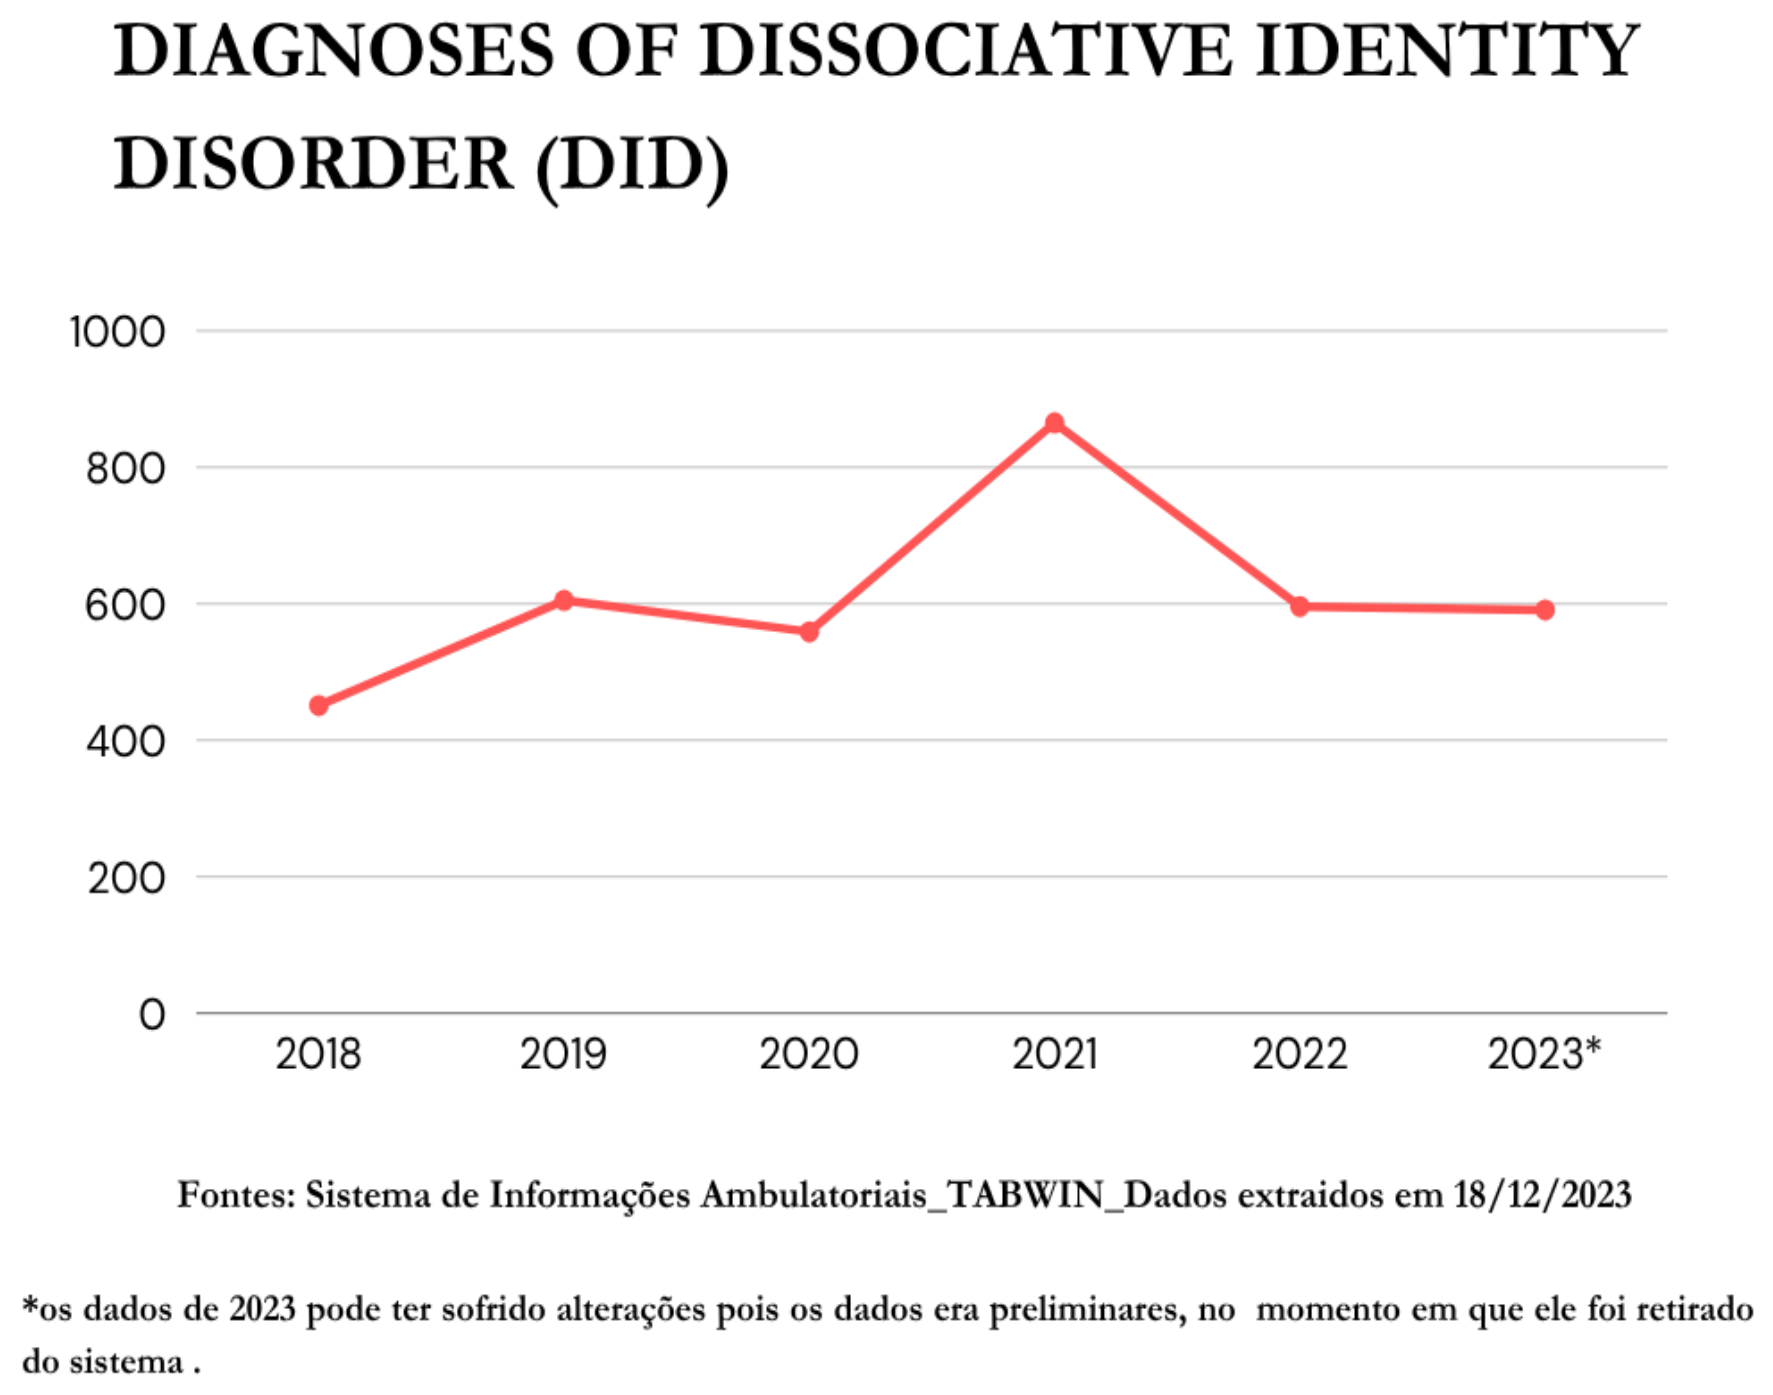
It is estimated that approximately 1.5% of the Brazilian population is affected by DID. According to data from Brazil's Ministry of Health, between 2018 and 2023, a total of 3,667 cases of other dissociative disorders (ICD-10 F44.8), including DID, were recorded in outpatient healthcare services, underscoring the epidemiological and clinical relevance of this condition [10].
Figure 1.
presents the annual variation in the number of reported cases between 2018 and 2023. (Brazil, Ministry of Health, 2023).
Figure 1.
presents the annual variation in the number of reported cases between 2018 and 2023. (Brazil, Ministry of Health, 2023).
The development of this article is grounded in the complexity and clinical relevance of Dissociative Identity Disorder (DID) within the fields of psychology and psychiatry. DID is a multifaceted condition characterized by a broad spectrum of symptoms and clinical presentations, posing significant challenges to both scientific research and professional practice.
From an academic perspective, this study seeks to contribute to reducing existing gaps in the specialized literature on DID. By providing a comprehensive analysis of its causes, clinical manifestations, and implications, the study aims to stimulate further research and expand current understanding of the disorder. Furthermore, its findings may support healthcare professionals in achieving more accurate diagnoses and implementing more effective therapeutic interventions, thereby directly benefiting individuals living with DID.
The social relevance of this study is equally significant. Individuals with DID frequently experience stigma and misunderstanding, factors that hinder social integration and limit access to appropriate mental healthcare. Expanding knowledge about the disorder may promote greater public awareness and empathy, contributing to the reduction of prejudice and fostering a more inclusive society. Such an enhanced understanding also has the potential to support the development of more effective mental health interventions and to inform public policies that ensure access to specialized services and continuous psychological support.
The primary objective of this study is to examine the clinical characteristics of DID and the psychological processes underlying the disorder. More specifically, it aims to identify the comorbidities most frequently associated with DID and to analyze how these conditions affect individuals' quality of life across personal, social, academic, and occupational domains.
It is expected that this research will contribute to a more comprehensive understanding of the psychological mechanisms underlying DID while promoting greater awareness and dispelling common misconceptions surrounding the disorder. By examining the impact of DID on individuals' lives, this study seeks to foster empathy and a deeper understanding of the challenges they face, ultimately contributing to the advancement of clinical practice, public policy, and social initiatives aimed at building a more inclusive, supportive, and compassionate society.
2. Materials and Methods
This study was conducted as a narrative, descriptive, and exploratory literature review with the aim of identifying, synthesizing, and critically analyzing the scientific literature on Dissociative Identity Disorder (DID). This methodological approach was selected to facilitate a comprehensive understanding of the disorder across its clinical, psychological, and social dimensions, while also identifying gaps in the existing literature that may guide future research.
The theoretical corpus was compiled through searches of multiple academic databases and scholarly search platforms, including Google Scholar, SciELO, and PePSIC, as well as scientific books and reference works in the fields of psychology and psychiatry. The search strategy employed predefined keywords, including Dissociative Disorders, Dissociative Identity Disorder, DID, Depersonalization, Schizophrenia, Dissociation, and their Portuguese equivalents.
The inclusion criteria comprised peer-reviewed articles, books, and scientific publications addressing DID, its clinical manifestations, associated comorbidities, and social implications, published in Portuguese, English, or Spanish. Studies lacking scientific rigor, publications not indexed in recognized academic databases, and opinion-based texts without adequate scholarly support were excluded.
It should be noted that two of the references included in this review were neither peer-reviewed journal articles nor academic books. Nevertheless, these sources underwent a rigorous critical appraisal and were found to meet the predefined criteria for quality, credibility, and relevance. In addition, the authors' academic and professional qualifications were verified, confirming that they were licensed psychologists or professionals with expertise in the field of psychology, thereby strengthening the reliability of these sources. Their inclusion was justified by their substantial contribution to understanding the topic, particularly in light of the limited number of scientific publications and the restricted diversity of available literature on Dissociative Identity Disorder. Consequently, these materials were incorporated following a careful methodological evaluation of their scientific relevance and informational value.
The selected literature was analyzed from three complementary perspectives. First, a narrative analysis was conducted to identify conceptual and clinical patterns across the studies. Second, a descriptive approach was employed to systematically summarize the principal characteristics and clinical manifestations of DID. Finally, an exploratory analysis was performed to identify knowledge gaps and generate hypotheses capable of informing future investigations.
To enhance the linguistic quality, clarity, and readability of the manuscript, artificial intelligence (AI)-assisted language tools were used exclusively for editorial support, including language refinement, stylistic improvement, and translation into academic English. The AI did not contribute to the study design, literature selection, data analysis, interpretation of findings, or scientific conclusions. All AI-assisted outputs were carefully reviewed, verified, and, where necessary, revised by the authors to ensure the accuracy, integrity, and fidelity of the scientific content. The authors assume full responsibility for the final version of the manuscript.
3. Discussion
The literature review demonstrated that Dissociative Identity Disorder (DID) is a highly complex psychopathological condition characterized by considerable clinical heterogeneity and a strong association with traumatic experiences, particularly those occurring during childhood. Across the studies reviewed, dissociation consistently emerged as the central psychological mechanism underlying the disorder, being directly associated with identity fragmentation and the presence of multiple self-states.
The findings indicate a high prevalence of psychiatric comorbidities among individuals with DID, particularly post-traumatic stress disorder (PTSD), mood disorders, anxiety disorders, personality disorders, and substance use disorders. In addition, somatic symptoms and functional neurological manifestations were frequently reported, further highlighting the multifaceted nature of the disorder. The reviewed studies suggest that this substantial symptom overlap contributes significantly to diagnostic challenges, often resulting in underdiagnosis or delayed diagnosis of DID.
Regarding the neurobiological aspects of the disorder, evidence from neuroimaging studies revealed significant structural alterations, particularly within the frontal regions of the brain, including reductions in gray matter volume, cortical thickness, and cortical surface area. These neuroanatomical changes were consistently associated with exposure to severe traumatic experiences, supporting the hypothesis that early-life adversity exerts a profound influence on neuropsychological development.
Furthermore, the findings indicate that DID substantially impairs overall functioning across multiple domains of life, including personal, social, academic, and occupational functioning. The reviewed literature describes marked difficulties in establishing and maintaining interpersonal relationships, emotional instability, disturbances in self-perception, and a high prevalence of self-destructive behaviors, including suicide attempts. More than 70% of individuals receiving outpatient treatment reportedly have a history of suicide attempts, underscoring the elevated suicide risk associated with the disorder.
From a diagnostic perspective, the reviewed studies emphasize the importance of carefully differentiating DID from other psychiatric conditions, including PTSD, mood disorders, schizophrenia, and personality disorders, given the considerable overlap in clinical symptoms. Accurate diagnosis requires a comprehensive clinical assessment that takes into account the presence of dissociative amnesia, discontinuity of identity, and other complex dissociative manifestations.
Finally, the findings suggest that although current therapeutic interventions do not provide a definitive cure for DID, they can substantially reduce dissociative symptoms and improve patients' quality of life. The literature consistently emphasizes the importance of integrative, trauma-informed, and multidisciplinary treatment approaches capable of addressing the complexity of the disorder and its multiple clinical dimensions.
Dissociative Identity Disorder
Dissociative Identity Disorder (DID) was historically associated with supernatural explanations, particularly demonic possession, an interpretation that persisted until the nineteenth century. However, advances in medicine led to a paradigm shift in the understanding of this condition, replacing supernatural interpretations with a scientific and clinical framework [1].
In the early nineteenth century, Benjamin Rush emerged as one of the first physicians to provide a systematic clinical description of DID, outlining its fundamental characteristics. Subsequently, prominent psychiatrists such as Jean-Martin Charcot and Pierre Janet further advanced the understanding of the disorder by emphasizing its dissociative etiology [1]. During the same period, Sigmund Freud and Eugen Bleuler also contributed to the study of DID. Freud, from a psychoanalytic perspective, proposed that its symptoms originated from unconscious psychodynamic processes, whereas Bleuler associated the condition with schizophrenia [1]..
The clinical and social relevance of DID gradually increased due to several factors, including growing public awareness of childhood abuse and the widespread media coverage of landmark cases such as The Three Faces of Eve and Sybil. The case of Chris Costner Sizemore, whose life inspired The Three Faces of Eve, became particularly influential, especially following the birth of her daughter [1].
Chris Sizemore's case, internationally recognized through The Three Faces of Eve, is considered a landmark in the history of DID. In one well-documented episode, one of her identity states, Eve Black, attempted to suffocate her newborn daughter but was prevented from doing so by another identity state, Eve White. During approximately twenty-five years of psychiatric follow-up involving eight different psychiatrists, a total of twenty-two distinct identity states were identified within her psychological functioning [3].
Similarly, the case of Shirley Ardell Mason, which inspired the character Sybil, gained international recognition through Flora Rheta Schreiber's book and became one of the most influential case reports in the history of DID research. The book, later adapted into two films, explores Shirley's life and highlights the relationship between childhood sexual abuse and the subsequent development of dissociative pathology. Although aspects of the case remain the subject of scholarly debate regarding their historical accuracy, the Sybil case played a pivotal role in increasing awareness of dissociative phenomena within the context of DID [4,5].
Dissociative Identity Disorder is a complex psychopathological condition whose core feature is the profound fragmentation of the self as a primary defensive response to overwhelming early-life trauma. This process results in the coexistence of multiple self-states or identity configurations that remain psychologically fragmented and insufficiently integrated within the individual's personality structure. Each identity state may possess its own autobiographical memories, behavioral patterns, and, in extreme cases, distinct psychophysiological manifestations, reflecting a profound disruption in the integration of self-representation and the development of a cohesive ego structure [1,7,8,11].
DID extends far beyond the mere presence of multiple identities and is currently understood as a chronic and highly complex dissociative disorder. This fragmentation of psychological functioning is frequently accompanied by a range of comorbid conditions that, from a psychoanalytic perspective, may be interpreted as manifestations of repressed psychic material or hysterical conversion. These include dissociative amnesia, dissociative fugue, and functional neurological symptoms such as psychogenic non-epileptic seizures and psychogenic blindness. This broad spectrum of clinical manifestations contributes to the considerable complexity of DID and substantially impairs an individual's ability to maintain stable psychological functioning and adaptive performance across personal, social, academic, and occupational domains.
Given this complexity, several authors have proposed replacing the current terminology with broader designations such as Major Dissociative Disorder, Pervasive Dissociative Disorder, or Complex Dissociative Disorder. These proposed terms are intended to more accurately reflect the multidimensional nature of the disorder, which extends beyond the simple coexistence of multiple identity states. Within this framework, identity switching is no longer regarded as the central diagnostic feature; instead, greater emphasis is placed on identifying and treating the broad range of associated dissociative symptoms and psychiatric comorbidities [1,7,8,9].
Dell [6] states:
"Over the past several decades, it has become increasingly evident that Dissociative Identity Disorder (DID) is characterized by far more than the presence of 'alters.' Individuals with DID routinely exhibit a broad range of dissociative symptoms. In other words, DID is more than a disorder of multiple identities; it is a chronic and complex dissociative disorder" (p. 392).
Clinical studies indicate that Dissociative Identity Disorder (DID) is diagnosed more frequently in women than in men, with reported female-to-male ratios ranging from 5:1 to 9:1. [1] This higher prevalence among women, together with other distinctive features of the disorder, has been the subject of extensive investigation.
Psychologist Valéria Barbieri notes that DID may manifest in ways that resemble states of possession, in which individuals perceive their own volition as being overridden by an external force. However, it is essential to distinguish these manifestations from those associated with religious or spiritual practices, as experiences in DID are involuntary, distressing, and occur outside culturally sanctioned religious contexts [12]. The Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR) reinforces this distinction by emphasizing that DID should not be equated with culturally or religiously accepted practices [8].
The analogy between DID and a "mind virus" is frequently employed to illustrate the intrusive and debilitating nature of the disorder. Similar to the way a virus affects the human body, DID may appear to "take control" of an individual's mental functioning, limiting conscious control over thoughts, emotions, and behavior. Although there is currently no definitive cure for DID, therapeutic interventions can substantially reduce dissociative symptoms and improve patients' quality of life.
The absence of appropriate treatment may result in significant psychological and physical consequences. Individuals with DID are at increased risk of developing psychiatric comorbidities, including substance use disorders involving both legal and illicit substances, as well as engaging in self-destructive behaviors, including suicide attempts [8,12].
With regard to Dissociative Identity Disorder in children, the presence of clearly differentiated identity states is relatively uncommon. Nevertheless, affected children frequently exhibit difficulties with concentration, the development of interpersonal relationships, and the expression of traumatic experiences through play [12]. According to the DSM-5-TR, children with DID typically do not display overt identity switching; instead, they may present with imaginary companions, seemingly autonomous behaviors, or personified mood states. The manual further emphasizes that these symptoms cannot be adequately explained by normal imaginative play or the presence of imaginary friends alone [8].
During adolescence, DID often becomes the focus of clinical attention because of the emergence of symptoms such as suicidal behaviors and abrupt behavioral changes, which are frequently misdiagnosed as attention-deficit/hyperactivity disorder (ADHD) or pediatric bipolar disorder. The DSM-5-TR also notes that some children and adolescents with DID may exhibit aggressive behavior and marked irritability [8].
A classic clinical example of Dissociative Identity Disorder is the case reported by Martínez-Taboas (1995) in Puerto Rico. Reproduced in Basic Psychiatry by Louzã Neto and Elkis [13], this case illustrates several of the clinical and phenomenological features of DID.
Diana was a 26-year-old Puerto Rican woman, the mother of two children, who worked in an office. She sought psychological treatment complaining of dizziness, episodes of loss of consciousness, and seizures. During the clinical interview, she was also found to exhibit episodes of dissociative amnesia, headaches, auditory hallucinations (hearing her name being called), and pronounced mood fluctuations. She had a history of severe physical abuse by her mother during childhood and had been raped by her boyfriend during adolescence. During psychotherapy, Diana occasionally manifested two distinct identity states. Manuel was cooperative and supportive toward both Diana and the therapist, whereas Esther was aggressive, hostile, and frequently interfered with the therapeutic process. The handwriting of Manuel and Esther differed from Diana's own handwriting. Although psychotherapy had begun to foster improved communication and cooperation between Manuel and Esther, treatment was discontinued when Diana and her husband relocated to the United States [13] (p. 293).
Psychopathological Aspects
Dissociative disorders are characterized by disruptions in the normal integration of consciousness, memory, identity, and other cognitive functions. This breakdown in the usual coherence of mental functioning may significantly impair multiple areas of life, ranging from interpersonal relationships and social functioning to academic and occupational performance [8].
A defining feature of Dissociative Identity Disorder (DID) is the presence of two or more distinct identity states or personality states, each characterized by its own patterns of perception, autobiographical memories, emotional responses, and behavioral repertoire.
Dissociative amnesia is characterized by an inability to recall important autobiographical information, most commonly related to traumatic or highly stressful experiences, that cannot be explained by ordinary forgetting.
Depersonalization/Derealization Disorder is characterized by persistent or recurrent experiences of detachment from oneself (depersonalization) or from one's surroundings (derealization), often accompanied by the subjective feeling of observing oneself or the external world from an outside perspective.
Other Specified Dissociative Disorder (OSDD) and Unspecified Dissociative Disorder (UDD) refer to clinical presentations involving prominent dissociative symptoms that cause clinically significant distress or functional impairment but do not fully meet the diagnostic criteria for the specific dissociative disorders defined in the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR) [8].
Relationship with trauma. Dissociative disorders, particularly DID, are strongly associated with traumatic experiences occurring during childhood or adolescence. Severe psychological trauma may trigger dissociative processes as adaptive defense mechanisms that enable individuals to cope with overwhelming emotional distress. However, it is important to emphasize that exposure to traumatic experiences alone does not inevitably lead to the development of dissociative disorders, indicating that additional biological, psychological, and environmental factors contribute to their etiology.
Common symptoms. In addition to the manifestations specific to each dissociative disorder, individuals with dissociative disorders may experience a range of common symptoms, including:
- Flashbacks: vivid and intrusive re-experiencing of traumatic events.
- Apathy: diminished interest, motivation, or emotional responsiveness.
- Altered perception of time: subjective experiences in which time appears to pass unusually quickly or unusually slowly.
The paradigmatic dissociative psychopathology. Dissociative Identity Disorder (DID) is widely regarded as the most complex of the dissociative disorders and frequently co-occurs with other dissociative conditions, particularly dissociative amnesia and depersonalization/derealization disorder. The distinct identity states, commonly referred to as alters, emerge as adaptive responses to overwhelming trauma and may assume specific psychological functions within the individual's internal organization [1,8].
According to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR), the expression of different identity states in individuals with DID varies considerably and is influenced by multiple factors, including social context, psychological stress, and individual characteristics. In certain situations, particularly in presentations involving experiences interpreted as possession by external entities, transitions between identity states may become more readily observable. However, most individuals with DID do not overtly display these transitions and instead conceal them or express them in subtle ways. Likewise, the presence of identity states with markedly distinct names, personal styles, or specific abilities is less common than is often assumed and does not constitute an essential diagnostic criterion.
Identifying distinct identity states may be particularly challenging because transitions often occur abruptly and internally without obvious external manifestations. Consequently, comprehensive psychological assessment plays a crucial role in detecting sudden disruptions in identity, alterations in self-experience, and changes in the perception of reality that are characteristic of Dissociative Identity Disorder [8].
Each identity state in DID represents a unique and complex psychological organization, possessing its own aspirations, preferences, autobiographical history, and even a distinct psychological age. Some identity states may remain psychologically fixed at the developmental period during which they originated, whereas others continue to evolve over time. These identity configurations may differ with respect to gender, age, ethnicity, and lived experiences.
The coexistence of multiple identity states gives rise to a highly complex and multifaceted psychological structure in which each identity fragment contributes to the individual's overall psychological organization. This complexity is reflected in the coexistence of distinct autobiographical memories, emotional experiences, interpersonal relationships, and behavioral patterns that together constitute the individual's dissociative system [1,14,15,16].
Under certain circumstances, DID may also be associated with physiological differences between identity states, including distinct allergic responses to specific foods and variations in dermatological conditions [17].
Speech patterns, hand gestures, and facial expressions may also differ substantially across identity states [9].
In a neuroimaging study conducted by Chalavi et al. [18], individuals diagnosed with Dissociative Identity Disorder comorbid with Post-Traumatic Stress Disorder (DID-PTSD) exhibited significant structural brain alterations compared with healthy controls. The findings demonstrated a significant reduction in total gray matter volume within the frontal lobe (p = 0.002), as well as significant differences in both the left (p = 0.006) and right frontal lobes. Furthermore, cortical surface analyses revealed an overall reduction in frontal lobe surface area, accompanied by an increase in the surface area of the right frontal lobe. A significant reduction in cortical thickness of the left frontal lobe was also observed [18].
Reinders et al. [19] demonstrated that bilateral gray matter volume in the superior frontal gyrus is significantly lower in individuals with Dissociative Identity Disorder (DID) than in healthy control participants. Additionally, reductions in cortical thickness (CT) and cortical volume (CV) were observed in the right superior frontal gyrus, whereas the left superior frontal gyrus exhibited decreases in CT, cortical surface area (SA), and CV [20,21].
The reduction of gray matter across several frontal brain regions—including Broca's area, the anterior cingulate cortex, and deeper cingulate regions—in individuals with DID supports the hypothesis that severe traumatic experiences exert adverse effects on the development of the frontal cortex [21,22,23]. In contrast, increased gray matter volume has been reported in the left superior frontal sulcus despite bilateral reductions identified in the same region by other neuroimaging studies [20,21].
Sussman et al. [21] and Reinders et al. [19,20] identified reductions in cortical gray matter volume across multiple regions of the frontal lobe, including the superior medial frontal gyrus, middle frontal gyrus, inferior frontal gyrus, and frontal pole, in both cerebral hemispheres.
Reinders et al. [20] also reported reductions in cortical surface area and cortical gray matter volume within the rostral middle frontal gyrus, particularly in the right hemisphere, as well as decreased cortical volume and cortical thickness of the left precentral gyrus in individuals with DID [19,20].
Neuroimaging investigations have consistently demonstrated marked reductions in gray matter volume, cortical thickness, and cortical surface area across several frontal brain regions in individuals with DID. Specifically, the pars triangularis and pars orbitalis exhibited reduced gray matter volume and cortical surface area in the right hemisphere, whereas the pars opercularis showed concurrent reductions in gray matter volume and cortical thickness in the left hemisphere. Reinders et al. [19,20] and Sussman et al. [21] consistently reported decreased cortical gray matter volume in multiple orbitofrontal regions, including the left lateral orbitofrontal cortex, the bilateral medial orbitofrontal cortex, and the bilateral dorsolateral prefrontal/middle frontal cortex.
Findings regarding the precuneus and the postcentral gyrus have been heterogeneous across neuroimaging studies. Irle et al. [24] found no significant structural differences in the precuneus among individuals with Borderline Personality Disorder (BPD), Dissociative Identity Disorder (DID), and healthy controls (HC). In contrast, Reinders et al. [20] reported increased cortical volume in the left precuneus and reduced cortical thickness in the right precuneus among patients with DID. With respect to the postcentral gyrus, Irle et al. [24] observed increased total and left hemispheric gray matter volume, whereas Reinders et al. [19,20] identified bilateral reductions in cortical volume within this region.
Strasburger and Waldvogel [9] presented the clinical case of a woman diagnosed with Dissociative Identity Disorder, referred to as BT, about whom the authors reported the following:
"In certain identity states, BT was able to communicate only in English; in others, only in German; and in still others, she spoke both languages. During childhood, she spent several years in an English-speaking country, where she spoke exclusively English. These observations were consistent with the records from the psychiatric clinic where she had received treatment prior to psychotherapy, as well as with collateral anamnestic reports provided by third parties, including the patient's friends."
In their case analysis, Strasburger and Waldvogel [9] describe the clinical course of a visually impaired woman diagnosed with Dissociative Identity Disorder (DID), highlighting a remarkable phenomenon. During one psychotherapy session, while manifesting an identity state corresponding to an adolescent male, the patient—who ordinarily relied on a guide dog for mobility—demonstrated the ability to read complete words from a magazine. Interestingly, this visual ability was initially restricted to the recognition of whole words, without the capacity to identify the individual letters composing them. Over time, this ability expanded to include the recognition of other visual stimuli, such as objects, and, through the use of hypnotic techniques, was generalized to additional identity states. At one point, multiple identity states were observed to coexist, some possessing visual perception and others lacking it, with rapid alternation between these states occurring within seconds.
Individuals diagnosed with Dissociative Identity Disorder (DID) frequently present with a broad spectrum of symptoms, including somatic manifestations and depressive episodes. In addition, psychotic symptoms, particularly auditory hallucinations, are commonly reported and may be related to the unconscious activity of distinct dissociated identity states, as proposed by Maraldi [7] .
Individuals with DID generally have a history of severe childhood trauma, particularly involving physical and sexual abuse, with prevalence estimates ranging from 85% to 97% of cases [1] . Although the potential contribution of genetic factors remains under investigation, there is currently no consistent evidence supporting a significant genetic influence on the development of DID. Historically, childhood abuse has been regarded as the primary etiological factor underlying the disorder, acting as the principal trigger for the emergence of dissociative symptoms. More recent research, however, including studies by Cardeña [25] and Gleaves et al. [26], suggests that traumatic experiences occurring during adulthood, such as those associated with natural disasters or armed conflict, may also precipitate dissociative symptoms [1,25,26] . According to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR), individuals with Dissociative Identity Disorder frequently experience difficulty recognizing or communicating alterations in their states of consciousness, memory lapses, and other dissociative manifestations. Flashbacks are common and are characterized by the intense re-experiencing of traumatic events, often accompanied by identity state transitions, derealization, and amnesia for the episodes. The life histories of these individuals are typically marked by complex developmental trauma, including physical, sexual, and emotional abuse, as well as exposure to highly stressful experiences during childhood. Non-suicidal self-injury is also frequently observed. Furthermore, individuals with DID tend to exhibit greater hypnotic susceptibility and a high capacity for dissociation, suggesting an increased predisposition to dissociative experiences. The DSM-5-TR also notes that some individuals may experience transient psychotic episodes [8,27].
Individuals with Dissociative Identity Disorder often display complex personality patterns characterized by social withdrawal and significant difficulties in establishing and maintaining meaningful interpersonal relationships. In some cases, a pronounced preference for social isolation may be observed. Borderline personality features, including impulsivity, emotional instability, and self-destructive behaviors, are common, particularly during periods of psychological crisis. Interpersonal relationships are frequently marked by ambivalence, characterized by the coexistence of a strong desire for closeness and an intense fear of abandonment. Despite these challenges, many individuals are able to establish interpersonal relationships, although these are often characterized by dysfunctional or abusive dynamics. Notably, obsessive personality traits appear to be more prevalent in DID than histrionic characteristics, although some individuals may also exhibit narcissistic or antisocial personality features [8].
Individuals with Dissociative Identity Disorder are at a markedly increased risk for suicidal behavior. More than 70% of patients receiving outpatient treatment report a history of suicide attempts, frequently accompanied by other forms of self-destructive behavior. This heightened vulnerability reflects a complex interaction of multiple risk factors, including severe and recurrent lifetime trauma, a high prevalence of post-traumatic stress disorder (PTSD), depressive disorders, and substance use disorders. Dissociation itself constitutes an independent risk factor for suicidal behavior, and the severity of dissociative symptoms has been shown to correlate directly with the frequency of suicide attempts and non-suicidal self-injurious behaviors [8,27].
Comorbidities and Differential Diagnosis
Individuals with Dissociative Identity Disorder (DID) frequently exhibit a high likelihood of developing additional psychiatric disorders as a result of the complex interaction between dissociative symptoms and other psychopathological conditions. The most prevalent comorbidities include post-traumatic stress disorder (PTSD), mood disorders such as major depressive disorder and bipolar disorder, anxiety disorders, including obsessive-compulsive disorder (OCD), eating disorders, psychotic disorders, personality disorders, substance use disorders, sleep disorders, and other dissociative disorders. Somatic symptoms and functional neurological manifestations are also commonly observed [8,27].
The complexity of DID, together with its substantial symptom overlap with other psychiatric conditions, may complicate the establishment of an accurate diagnosis. The Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR) emphasizes the importance of distinguishing DID from other disorders with similar clinical presentations, including the following:
Post-Traumatic Stress Disorder (PTSD). Both DID and PTSD are characterized by dissociative symptoms, including amnesia and intrusive recollections. However, in DID, dissociation is primarily associated with fragmentation of identity, whereas in PTSD it is generally understood as a response to traumatic experiences. Furthermore, intrusive experiences in DID may originate from different identity states, while in PTSD they are more directly linked to the traumatic event itself [8,27].
Mood Disorders. Comorbidity with mood disorders, particularly major depressive disorder and bipolar disorder, is common among individuals with DID. Nevertheless, mood fluctuations in DID are typically associated with transitions between different identity states, whereas mood changes in bipolar disorder follow a more cyclical course and are generally unrelated to alterations in identity [8,27].
Personality Disorders. The co-occurrence of DID and personality disorders, particularly Borderline Personality Disorder (BPD), is frequently reported. However, the apparent personality changes observed in DID result from the presence of multiple identity states, whereas personality disorders are characterized by relatively stable, pervasive, and enduring patterns of cognition, affect, and behavior that persist across time and situations [8,27].
Psychotic Disorders. Dissociative symptoms may mimic psychotic phenomena, including hallucinations and delusions, potentially leading to diagnostic confusion with disorders such as schizophrenia. However, in DID, these manifestations are more closely related to the fragmentation of identity and dissociative processes than to persistent delusional beliefs or primary psychotic pathology [8,27].
Dissociative Amnesia. Although both DID and Dissociative Amnesia involve significant memory disturbances, Dissociative Identity Disorder is distinguished by the presence of multiple identity states. In Dissociative Amnesia, memory loss is typically associated with a specific traumatic event, whereas in DID, amnestic episodes frequently occur between different identity states [8].
Depersonalization/Derealization Disorder. Both disorders involve experiences of detachment from oneself or one's surroundings. However, in DID, these experiences are frequently associated with transitions between multiple identity states, whereas in Depersonalization/Derealization Disorder the individual's sense of identity and overall reality testing generally remain intact despite persistent feelings of detachment [8].
Major Depressive Disorder. Major depressive disorder is a common comorbidity among individuals with DID. Nevertheless, fluctuations in mood are often associated with transitions between different identity states rather than representing independent depressive episodes. Furthermore, the anniversary reaction—an intense emotional response occurring around the anniversary of the original traumatic event—may resemble Seasonal Affective Disorder or recurrent depressive episodes but is more commonly observed within the context of dissociative disorders, particularly DID [8].
Substance-/Medication-Induced Disorders. Substance misuse is common among individuals with DID. However, the amnesia associated with acute intoxication or chronic substance use is generally attributable to the pharmacological effects of the substance and may improve following sustained abstinence. In contrast, dissociative amnesia in DID tends to be more persistent and is intrinsically related to the fragmentation of identity [8,28].
Post-Traumatic Amnesia Secondary to Traumatic Brain Injury (TBI). Dissociative Identity Disorder and traumatic brain injury (TBI) may both present with memory disturbances. However, TBI is typically associated with additional neurological manifestations, including loss of consciousness, disorientation, confusion, and, in more severe cases, significant neurological deficits. The neurocognitive disorders associated with TBI emerge immediately after the injury or upon recovery of consciousness and generally persist beyond the acute phase. Cognitive impairment following TBI may involve deficits in complex attention, executive functioning, learning and memory, processing speed, and social cognition. Although depersonalization may occasionally occur after TBI, it is not considered a characteristic clinical feature. These neurocognitive abnormalities help distinguish TBI from the dissociative amnesia observed in DID. In contrast, dissociative amnesia in DID is characterized by marked disruptions in the continuity of identity, autobiographical memory, and the sense of agency, features that are not typically observed following traumatic brain injury [8].
Functional Neurological Symptom Disorder (FNSD) differs from Dissociative Identity Disorder (DID) in that it is not characterized by the presence of multiple identity states and presents a distinct pattern of memory impairment. In DID, amnesia is typically more pervasive and functions as a psychological defense against traumatic experiences, whereas in FNSD, memory disturbances are more closely associated with functional neurological symptoms, such as psychogenic nonepileptic seizures [8].
Individuals who feign Dissociative Identity Disorder (DID) tend to emphasize its most conspicuous and widely recognized features, such as pronounced amnesia and dramatic behavioral changes, while overlooking the more subtle and characteristic manifestations of the disorder. Unlike individuals with genuine DID, who often experience considerable distress, shame, and impairment related to their symptoms, malingerers may display apparent indifference or even satisfaction regarding the diagnosis. In some cases, they may actively encourage the therapist to identify traumatic memories or stereotypical alternative identity states accompanied by conveniently timed episodes of amnesia. Simulated identity states are typically limited in number, highly stereotyped, and characterized by exaggerated behavioral changes that are usually displayed only in situations of observation or evaluation. In certain instances, individuals may construct opposing identities—for example, a "good" identity and a "bad" identity—to obtain secondary gain, such as avoiding personal responsibility or evading criminal liability [8,29,30].
As with other presentations involving malingering, a careful clinical and forensic assessment is essential to determine whether external incentives may be motivating the intentional production or exaggeration of symptoms [29].
Within the field of forensic psychology, professionals are frequently called upon to provide technical support to judges, juries, and legal counsel by presenting and interpreting scientific evidence regarding the symptoms of mental disorders, including dissociative disorders, thereby assisting judicial decision-making in criminal proceedings [29,30] .
In this context, Brand et al. [31,32], in a two-part review, provide practical guidelines and technical recommendations for clinicians specializing in dissociative disorders regarding the assessment of DID symptoms and their potential relationship to allegations of abuse involving criminal defendants. The authors emphasize the importance of thoroughly investigating the victim's history of childhood and adult trauma, as well as documenting previous dissociative symptoms and episodes. They also note that some individuals may be reluctant to disclose experiences of abuse or acknowledge the presence of a mental disorder. According to the authors, inadequate understanding of DID by judges or jurors may result in erroneous conclusions that genuine symptoms represent malingering, when, in fact, the clinical presentation is legitimate and can be reliably diagnosed by qualified mental health professionals. Brand et al. further argue that expert testimony should address the neurobiological aspects of DID and their implications for the individual's health, psychosocial functioning, prognosis, and the long-term healthcare costs associated with this chronic disorder [31,32].
However, the two-part review by Brand et al. [31,32], has been criticized by Merckelbach and Patihis [33]. These authors argue that Brand and colleagues place undue emphasis on the trauma model as the sole explanatory framework for Dissociative Identity Disorder (DID), while giving insufficient consideration to alternative theoretical perspectives, such as the fantasy model. Merckelbach and Patihis [33] further highlight the potential for reporting biases that may compromise the reliability of symptom reports, particularly in the presence of personal or contextual incentives, including financial gain or retaliatory motives. They cite evidence indicating that individuals reporting dissociative amnesia may also exhibit generalized symptom exaggeration, potentially with the intention of convincing evaluators that they have a mental disorder. Although these findings do not invalidate reports of dissociative amnesia, they underscore the importance of conducting thorough and methodologically rigorous clinical assessments. Based on the available scientific literature, the authors estimate that the false-positive rate for the diagnosis of DID ranges from approximately 10% to 30% of cases [30,33].
To minimize bias and improve diagnostic accuracy, the use of multiple sources of information is recommended. The assessment process should incorporate the individual's self-report while also integrating data obtained from standardized psychological testing, collateral interviews with family members, and other secondary informants. In addition, relevant documentation,including medical records, police reports, and other pertinent records, should be carefully reviewed whenever available.
The authors conclude by emphasizing that DID is associated with a wide range of potential contributing factors, encompassing traumatic experiences, sleep disturbances, emotional dysregulation, and the intentional feigning of symptoms. Accordingly, all plausible explanatory hypotheses should be evaluated in an objective and impartial manner. In response to these criticisms, Brand et al. [31,32] published a formal rebuttal challenging the assumptions advanced by Merckelbach and Patihis [33] and presenting additional empirical evidence supporting the trauma model of DID [30,33].
From this perspective, before criminal sanctions are imposed, it is essential to establish a reliable diagnosis of Dissociative Identity Disorder in the accused individual, thereby enabling the application of an individualized and equitable sentence consistent with the legal principle of individualized sentencing. Specialized training for forensic psychologists and professionals within the Brazilian judicial system is therefore essential to ensure fair and evidence-based decision-making in cases involving this psychopathology. Such cases require individualized evaluation and close interdisciplinary collaboration with mental health professionals to ensure that clinical evidence is appropriately integrated into judicial proceedings [30,33].
The Impact of Dissociative Identity Disorder on the Lives of Affected Individuals
Dissociative Identity Disorder (DID) is a psychiatric condition that profoundly impairs the quality of life of affected individuals, exerting substantial effects on their social relationships as well as their personal and occupational functioning. These impairments arise primarily from difficulties in establishing and maintaining interpersonal relationships and from disturbances in self-perception. The different identity states exhibit a relative degree of autonomy, each possessing its own experiences, lifestyle, preferences, and behavioral patterns. It is common for one identity state to have little or no awareness of the existence of the others [15].
The historical development of Dissociative Identity Disorder dates back to the nineteenth century, when the earliest clinical descriptions of the condition emerged. Although DID was formally recognized by the American Psychiatric Association (APA) in 1980, the disorder continues to be surrounded by considerable stigma, contributing to delayed diagnosis, limited access to appropriate therapeutic interventions, and the persistence of discriminatory attitudes within society. Insufficient public awareness and the persistence of misconceptions regarding DID further exacerbate the suffering experienced by affected individuals [8,15].
In Dissociative Identity Disorder, clinical manifestations are frequently associated with severe traumatic experiences, particularly physical and sexual abuse occurring during early psychological development. According to the developmental theories of Mahler, Winnicott, and Freud, this period is critical for the formation of the ego, the self, and object constancy. When exposed to profoundly disorganizing experiences during this stage of heightened psychological vulnerability, the psyche mobilizes highly complex defensive mechanisms, resulting in the development of multiple identity configurations. Each of these self-structures may function as a facilitating environment, providing the individual with an internal psychological framework sufficiently secure to keep traumatic experiences outside conscious awareness. This defensive process is sustained by mechanisms such as repression, which prevents painful material from entering consciousness, and splitting, which separates contradictory aspects of experience in order to preserve ego cohesion. In this way, the return of the repressed and the conscious re-experiencing of trauma are prevented. However, because dissociation impedes the integration of these experiences, it ultimately compromises the consolidation of a unified identity, resulting in fragmented self-perception and multiple psychosocial challenges throughout adulthood [15,34].
(; Mahler et al., 1986; Riani & Caropreso, 2019; Winnicott, 1965/1982, 1971/2019; Klein, 1937/2023.
Dissociation, understood both as a defense mechanism and as a manifestation of repression, may occur abruptly, producing either temporary or enduring divisions between psychic structures that affect the regulation of mental and psychomotor functions. This splitting of the ego disrupts the integrity of the narcissistic self-image and generates confusion in the constitution of the subject. Such psychodynamic processes further impair the development of object relationships, particularly in response to experiences that have not been symbolized or adequately elaborated, in which the individual lacks conscious control over his or her own thoughts, emotions, or behaviors [7].
5. Conclusions
The present literature review demonstrated that Dissociative Identity Disorder (DID) is a highly complex psychopathological condition characterized by considerable diagnostic challenges. Beyond the presence of multiple identity states, DID is frequently associated with a broad range of psychiatric comorbidities and, in many cases, with substance misuse. The complexity of its clinical presentation contributes to frequent diagnostic difficulties, as the disorder may be misidentified as schizophrenia or other psychiatric conditions, or clinicians may recognize only the associated comorbidities without identifying the underlying dissociative disorder.
The objectives of this study were achieved, providing a comprehensive understanding of the clinical characteristics of DID, its most common psychiatric comorbidities, and its impact on the quality of life of affected individuals. The findings consistently indicate substantial impairments across personal, social, academic, and occupational domains, in addition to high rates of psychological distress, self-injurious behavior, and suicide risk. These observations underscore the importance of early recognition and evidence-based clinical interventions.
One of the principal limitations encountered during the development of this review was the limited availability of Brazilian scientific literature addressing DID. Compared with the extensive international literature, particularly publications in English, research conducted in Brazil remains relatively scarce. This gap highlights the need for further national investigations to strengthen the scientific evidence base, improve professional training, and enhance clinical care for individuals living with DID.
From a public health perspective, the findings emphasize the importance of integrated strategies encompassing prevention, early diagnosis, and long-term treatment. Primary prevention should prioritize public policies aimed at preventing childhood physical, psychological, and sexual abuse while promoting safe and supportive family environments. Secondary prevention should focus on expanding access to specialized mental health services and improving the training of healthcare professionals in the recognition and assessment of dissociative disorders. At the tertiary level, comprehensive multidisciplinary follow-up—including psychiatric care, evidence-based psychotherapy, and appropriate management of psychiatric comorbidities, should be ensured according to each patient's individual clinical needs.
In conclusion, psychology and psychiatry play a fundamental role in the identification, understanding, and treatment of Dissociative Identity Disorder. Advancing scientific knowledge, improving the education and training of mental health professionals, and reducing the social stigma surrounding DID are essential to promoting earlier diagnosis, more effective interventions, and improved quality of life for affected individuals. It is hoped that this review will contribute to the growing body of scientific knowledge on DID and encourage further research into its psychopathological, neurobiological, and psychosocial mechanisms, thereby supporting the development of increasingly effective clinical practices and public health policies.
6. Patents
During the preparation of this manuscript, the authors used ChatGPT (OpenAI) to assist with language editing, refinement of the academic writing, and improvement of the overall clarity and organization of the text. The authors carefully reviewed and edited the generated content and take full responsibility for the content of this publication.
Abbreviations
The following abbreviations are used in this manuscript:
| SA | Surface Area |
| DID-PTSD | Dissociative Identity Disorder associated with Post-Traumatic Stress Disorder |
| DID | Dissociative Identity Disorder |
| BPD | Borderline Personality Disorder |
| HC | Control group |
| CT | Cortical thickness |
| CV | Cortical volume |
| TABWIN | A tabulation software developed by DATASUS that allows users to process SUS data files, perform statistical calculations, cross-reference variables, and generate charts or maps. Researchers and health managers use TabWin alongside data files (such as monthly outpatient production records) to extract specific figures for healthcare visits by region, period, or ICD-10. |
| SIA (Outpatient Information System) | The official system of DATASUS (Ministry of Health) that records all visits, procedures, and treatments performed within the SUS outpatient network. |
| The pars triangularis | is defined as a part of the inferior frontal gyrus, located between the anterior ramus of the lateral sulcus and the pars opercularis. It is commonly associated with Broca's area, which is involved in speech production and language processing. |
| The pars orbitalis | is defined as the portion of the orbicularis oculi muscle responsible for eyebrow movement, acting specifically as one of the primary eyebrow depressors through its superomedial fibers. |
| The precuneus | is a highly developed region of the medial parietal cortex, involved in the control of voluntary shifts of attention, the retrieval of episodic memories, personal identity, and past experiences. It is associated with the highest resting perfusion rate in the cerebral cortex and plays a role in spatially guided behavior and the imagination of one's own actions. |
References
- Sadock, B. J.; Sadock, V. A.; Ruiz, P. Compêndio de psiquiatria (E-book). Grupo A; 2017; Available online: https://integrada.minhabiblioteca.com.br/#/books/9788582713792/.
- Panitz, G. D. O.; Mendes, M. V.; Monteiro, R. T.; Gonçalves, E. P.; DOS ANJOS, G. U. I. L. H. E. R. M. E.; TORREZ, V. R.; PACHECO, M. A. Por onde anda a histeria? Acta Méd. 2018, 359–367. [Google Scholar]
- Acevedo, Andrea. ¿Cómo se originan las múltiples personalidades? Explora el trastorno de identidad disociativo y su gravedad. Cinco Noticias. 17 nov 2022. Available online: https://www.cinconoticias.com/multiples-personalidades/.
- Cazabat, E. H. Del trastorno por estrés postraumático a la disociación. Um espectro de respuestas al trauma. Revista de Psicotrauma. 2003. Available online: https://www.psicotrauma.com.ar/cazabat/archivos/21-Cazabat-Del%20trastorno%20por%20estrés%20postraumático%20a%20la%20disociacion.pdf.
- Montanari, C. C. Sybil: discutindo um caso de Transtorno Dissociativo de Identidade. Saúde Em Redes 2021, 7(2), 269–273. [Google Scholar] [CrossRef]
- Dell, P. F. 24 The Long Struggle to Diagnose Multiple Personality Disorder (MPD). Dissociation Dissociative Disord. DSM-V. Beyond 2009, 383. [Google Scholar]
- Maraldi, E. D. O. Transtorno dissociativo de identidade: aspectos diagnósticos e implicações clínicas e forenses. Rev. Front. Interdiscip. Do Direito 2019, 1(2), 32. [Google Scholar] [CrossRef]
- American Psychiatric Association. Manual diagnóstico e estatístico de transtornos mentais: DSM-5-TR – Texto revisado (E-book). Grupo A. 2023. Available online: https://integrada.minhabiblioteca.com.br/#/books/9786558820949/.
- Strasburger, H.; Waldvogel, B. Sight and blindness in the same person: Gating in the visual system. PsyCh. J. 2015, 4(4), 178–185. [Google Scholar] [CrossRef]
- Brasil. Ministério da Saúde. Registro de atendimentos ambulatoriais por CID-10: Sistema de Informações Ambulatoriais (SIA) – TABWIN [Base de dados]. Data de extração. 2023.
- Faria, M. d. A. O TESTE DE PFISTER E O TRANSTORNO DISSOCIATIVO DE IDENTIDADE. Avaliação Psicológica 2008, 7(3), 359–370. Available online: https://www.redalyc.org/pdf/3350/335027185009.pdf.
- Pierri, Vitória; Barbieri, Valéria. Ambiente seguro e estável para a criança ajuda a prevenir transtorno de identidade: Valéria Barbieri comenta sobre o transtorno dissociativo de identidade, conhecido como “personalidade múltipla”, relacionado a traumas sofridos na infância, facilitando a manifestação de duas ou mais personalidades. Jornal da USP, Ribeirão Preto, São Paulo, Brasil;Atualidades. 5 nov 2021. Available online: https://jornal.usp.br/atualidades/ambiente-seguro-e-estavel-para-a-crianca-ajuda-a-prevenir-transtorno-de-identidade/.
- Louzã Neto, M. R.; Elkis, H. Psiquiatria básica, 2ª ed.; Artmed, 2007. [Google Scholar]
- Kohlenberg, R. J.; Tsai, M. Psicoterapia analítica funcional: Criando relações intensas e curativas; ESETec, 1991. [Google Scholar]
- Gulisz, I. C.; Vieira, F. d. M. Um Estudo de Revisão Sobre o Transtorno Dissociativo de Identidade: Características e Direções de Tratamento. Rev. PsicoFAE Plur. Em Saúde Ment. 2022, 11(1), 71–83. [Google Scholar] [CrossRef]
- International Society for the Study. Guidelines for Treating Dissociative Identity Disorder in Adults, Third Revision. J. Trauma Dissociation 2011, 12(2), 115–187. [Google Scholar] [CrossRef]
- Levin, R. The body and modernity in MPD/DID. In Broken images, broken selves: Dissociative narratives in clinical practice; Krippner, S., Powers, S. M., Eds.; Brunner/Mazel, 1997; pp. 136–162. [Google Scholar]
- Chalavi, S.; Vissia, E. M.; Giesen, M. E.; Nijenhuis, E. R. S.; Draijer, N.; Barker, G. J.; Veltman, D. J.; Reinders, A. A. T. S. Similar cortical but not subcortical gray matter abnormalities in women with posttraumatic stress disorder with versus without dissociative identity disorder. Psychiatry Res. Neuroimaging 2015, 231(3), 308–319. [Google Scholar] [CrossRef]
- Reinders, A. A., Marquand, A. F., Schlumpf, Y. R., Chalavi, S., Vissia, E. M., Nijenhuis, E. R., ... & Veltman, D. J. (2019). Aiding the diagnosis of dissociative identity disorder: pattern recognition study of brain biomarkers. Br. J. Psychiatry 2019, 215(3), 536–544. [CrossRef]
- Reinders, A. A. T. S.; Marquand, A. F.; Schlumpf, Y. R.; Chalavi, S.; Vissia, E. M.; Nijenhuis, E. R. S.; Dazzan, P.; Jäncke, L.; Veltman, D. J. Aiding the diagnosis of dissociative identity disorder: pattern recognition study of brain biomarkers. Br. J. Psychiatry 2018, 215(3), 536–544. [Google Scholar] [CrossRef]
- Sussman, D.; Pang, E. W.; Jetly, R.; Dunkley, B. T.; Taylor, M. J. Neuroanatomical features in soldiers with post-traumatic stress disorder. BMC Neurosci. 2016, 17(1). [Google Scholar] [CrossRef]
- Blihar, D.; Delgado, E.; Buryak, M.; Gonzalez, M.; Waechter, R. A systematic review of the neuroanatomy of dissociative identity disorder. Eur. J. Trauma Dissociation 2020, 4(3), 100148. [Google Scholar] [CrossRef]
- Braxton, S. A. Reawakening Sekhmet: The experience of African American women survivors of childhood sexual abuse with Kemetic yoga practice. Doctor of Philosophy (Ph.D.), Saybrook University, 2017. Available online: https://www.yoga-als-therapie.de/assets/Studien/Downloads/Braxton-2017-Dissertation.pdf.
- Irle, E.; Lange, C.; Weniger, G.; Sachsse, U. Size abnormalities of the superior parietal cortices are related to dissociation in borderline personality disorder. Psychiatry Res. Neuroimaging 2007, 156(2), 139–149. [Google Scholar] [CrossRef]
- Cardeña, E. The etiologies of dissociation. Broken Images Broken Selves Dissociative Narrat. Clin. Pract. 1997, 61–87. [Google Scholar]
- Gleaves, D. H.; May, M. C.; Cardeña, E. An examination of the diagnostic validity of dissociative identity disorder. Clin. Psychol. Rev. 2001, 21(4), 577–608. [Google Scholar] [CrossRef]
- Macário de Almeida, A.; Belloli Ribeiro, A.; Benedetti, L. Transtorno Dissociativo de Identidade: um mecanismo de proteção complexo. Psicopatol. Crítica Perspect. Do Sofrimento Exist. 2020, 1(1). Available online: https://koan.emnuvens.com.br/psicopato/article/view/38.
- Pereira, F. R.; Xavier, F. Q.; Pavan, L. G.; Lopes, B.; Mendonça, A. B. L.; Machado, L.; de Sousa, C. Transtorno Dissociativo de Identidade. Anais Do II Congresso Médico De Rio Verde, 2019; p. 203. [Google Scholar]
- Scott, C. (Ed.) DSM-5® and the Law: Changes and Challenges; Oxford University Press, 2015. [Google Scholar]
- de Sousa, C. B. P.; Neto, F. M. R.; Braga, C. R. APLICAÇÃO DA LEI PENAL BRASILEIRA E O TRANSTORNO DISSOCIATIVO DE IDENTIDADE. Rev. Novos Desafios 2025, 5(1), 191–201. Available online: https://novosdesafios.inf.br/index.php/revista/article/view/144.
- Brand, B. L.; Schielke, H. J.; Brams, J. S. Assisting the Courts in Understanding and Connecting with Experiences of Disconnection: Addressing Trauma-Related Dissociation as a Forensic Psychologist, Part I. Psychol. Inj. Law 2017, 10(4), 283–297. [Google Scholar] [CrossRef]
- Brand, B. L.; Schielke, H. J.; Brams, J. S.; DiComo, R. A. Assessing Trauma-Related Dissociation in Forensic Contexts: Addressing Trauma-Related Dissociation as a Forensic Psychologist, Part II. Psychol. Inj. Law 2017, 10(4), 298–312. [Google Scholar] [CrossRef]
- Merckelbach, H.; Patihis, L. Why “Trauma-Related Dissociation” Is a Misnomer in Courts: a Critical Analysis of Brand et al. (2017a, b). Psychol. Inj. Law 2018, 11(4), 370–376. [Google Scholar] [CrossRef]
- Ferenczi, S. Confusão de linguagens entre o adulto e a criança. In Artes & Ecos; (Obra original publicada em 1933); Spieler, E., Ed.; 2025. [Google Scholar]
- Freud, S. Obras completas, volume 17: Inibição, sintoma e angústia, O futuro de uma ilusão e outros textos (1926 -1929); Obra original publicada em 1926; de Souza, P. C., Ed.; Companhia das Letras., 2014. [Google Scholar]
- Freud, S. Obras completas Volume 6: Três ensaios sobre a teoria da sexualidade, análise fragmentária de uma histeria ("O caso Dora" ) e outros textos; Obra original publicada em 1905; de Souza, P. C., Ed.; Companhia das Letras., 2016b. [Google Scholar]
- Mahler, M. s.; Pine, F.; Bergman, A. O Nascimento Psicologico da Criança - Simbiose e Individuação, 2a ed.; Russo, J. A., Ed.; 1986. [Google Scholar]
- Riani, A.; Caropreso, F. A teoria de Margaret Mahler sobre o desenvolvimento psíquico precoce normal. Psicol. Em Rev. 2019, 24(3), 894–914. [Google Scholar] [CrossRef]
- Winnicott, D. W. O Ambiente e os Processos de Maturação: Estudos Sobre a Teoria do Desenvolvimento Emocional; (Obra original publicada em 1965); Ortiz, I. C. S., Ed.; Artmed, 1982. [Google Scholar]
- Winnicott, D. W. O brincar e a realidade -; (Obra original publicada em 1971); Longhi, B., Ed.; Ubu Editora, 2019; vol. 1. [Google Scholar]
- Klein, M. Amor, culpa e reparação e outros ensaios; (Obra original publicada em 1937); Imago Editora: Ubu, 2023. [Google Scholar]
- Reinders, A. A. T. S.; Chalavi, S.; Schlumpf, Y. R.; Vissia, E. M.; Nijenhuis, E. R. S.; Jäncke, L.; Veltman, D. J.; Ecker, C. Neurodevelopmental origins of abnormal cortical morphology in dissociative identity disorder. Acta Psychiatr. Scand. 2017, 137(2), 157–170. [Google Scholar] [CrossRef]
- Negro Junior, P. J.; Palladino-Negro, P.; Louzã, M. R. Dissociação e transtornos dissociativos: modelos teóricos. Rev. Bras. De Psiquiatr. 1999, 21(4), 239–248. [Google Scholar] [CrossRef]
- Onocko-Campos, R. T. Saúde mental no Brasil: avanços, retrocessos e desafios. Cad. De Saúde Pública 2019, 35(11). [Google Scholar] [CrossRef]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.