

Submitted:
08 September 2026
Posted:
08 September 2026
You are already at the latest version
Abstract
Background: Large language models can support clinical work, but their use in high-stakes settings raises risks of over-reliance, opacity, and erosion of professional judgment. Objective: To present MAGI, a conceptual multipersona framework for ethical deliberation and criticality triage in clinical decision support. Approach: The proposal distinguishes constrained analytical personas from autonomous clinical agents and combines legal, personalist bioethical, and biomedical perspectives through a content-analysis-informed synthesis. No empirical implementation or validation results are reported. Proposed framework: A coordinator is intended to document relevant considerations, agreements, disagreements, evidentiary gaps, and reasons for escalation. The proposed output is an auditable deliberation report, not a treatment recommendation. Clinician review is required before any use; high-criticality cases or persistent material disagreement require escalation to the appropriate accountable human process. No convergence threshold or iteration count is established as a safety criterion. Conclusion: A multipersona architecture may help make value conflicts and automation-related risks visible before action is taken. Prospective evaluation is required to determine whether it improves issue detection, appropriate reliance, usability, or safety compared with simpler alternatives.
Keywords:
artificial intelligence
; clinical decision support
; bioethics
; automation bias
; human oversight
; multipersona systems
Introduction
Large language models have shown clinically relevant knowledge and reasoning capabilities in benchmarked medical question-answering tasks. However, current models retain important limitations in factuality, possible harm, bias, and alignment with clinical standards [1]. Reviews of artificial intelligence in medicine likewise describe substantial opportunities for improving access, diagnostic support, workflow, and personalization, while emphasizing the need to address validation, fairness, transparency, privacy, and implementation constraints [2,3]. These constraints are especially consequential when the system is used near a treatment decision, a time-sensitive emergency, or an ethically contested intervention.
A central human-factors concern is automation bias: the tendency to over-accept an automated recommendation or to omit an action because a system did not prompt it. The phenomenon can generate both commission and omission errors [4]. In healthcare, a systematic review found that inaccurate decision-support advice can contribute to erroneous decisions and that accountability, calibrated trust, and interface design can influence appropriate reliance [5]. The central safety question is therefore not only whether an artificial intelligence system can produce a plausible answer. It is when that answer should trigger structured human deliberation rather than further automation.
Professional expertise remains indispensable in this setting. Qualitative work on artificial intelligence and personalized medicine shows that clinicians and trainees commonly regard algorithmic tools as potentially useful additions to judgment, while expressing concern that they may undermine accumulated clinical insight, autonomy, and the relational dimension of care [6]. These findings support a design principle for clinical AI: it should expose uncertainty and preserve accountability rather than conceal disagreement behind a single fluent recommendation.
This article presents MAGI as a conceptual framework for ethical deliberation and criticality triage. MAGI is not a diagnostic model, a treatment recommender, or an autonomous clinical agent. It is an evaluative guardrail intended to organize distinct normative and biomedical considerations, document unresolved tensions, and indicate when a case requires direct human review. Here, criticality triage means identifying the required intensity of human review, not assigning patient acuity or prioritizing treatment. MAGI is proposed as a case-level deliberative component within broader AI governance, rather than a replacement for institutional governance guidance [7].
Conceptual Approach and Scope
This article is a conceptual design proposal, not a systematic review, consensus guideline, or empirical validation study. Its argument links automation-related risks [4,5] to distinct questions about professional duties, the moral status and preferences of the patient, and clinical evidence. The three analytical roles are design choices intended to separate these questions; their selection does not establish that they are exhaustive, optimal, or independently validated. The cited literature supplies conceptual and normative grounding, not evidence that MAGI is effective. Requirements described below are proposed specifications to be tested, not observations of system performance.
The MAGI framework evolved from an undergraduate research project begun in 2023 that compared responses from Ask Delphi and ChatGPT to CREMESP requests. Preliminary findings were presented at the ICB Congress in Porto, Portugal, in 2024; a more detailed analysis in 2025 examined thematic areas and criteria for strong and weak response consistency. These studies informed the current deliberative model. The selection and design of the personas were informed by specialists from the respective domains, but this process was not a formal consensus exercise. The preliminary studies are contextual to this proposal and are not reported here as clinical validation results.
The initial evaluation scope is clinician-facing analysis of standardized case descriptions and proposed interventions in simulation. Before any clinical study, the intended specialty, setting, users, languages, exclusions, review pathway, and acceptable response time must be specified prospectively. MAGI is not intended to manage emergencies or delay time-sensitive care. A deployment-specific risk assessment must determine whether an implementation is permissible and what ethical, legal, and regulatory review it requires.
Framework Purpose and Design Principles
MAGI is designed for clinical decision-support workflows in which a proposed action may affect patient safety, legal duties, professional ethics, or deeply held values. The proposed framework would accept a structured case description and a proposed intervention. It would then produce a deliberation report. The report is intended to identify relevant duties and values, state the factual or evidentiary uncertainties that limit confidence, record agreement and disagreement among the analytical perspectives, and specify the appropriate level of human review.
The framework follows five design principles. First, it is advisory: no MAGI output authorizes clinical action. Second, it is plural: disagreement among perspectives is treated as information rather than as an error to be optimized away. Third, traceability is a requirement: each report must preserve the inputs, domain analyses, synthesis, escalation decision, and any interruption. Fourth, thematic convergence is descriptive, not a measure of ethical truth, safety, or clinical validity; it must not determine escalation on its own. Fifth, a qualified clinician and, when indicated, an institutional ethics process retain responsibility for the decision.
Multipersona Architecture
The word persona is used deliberately. In the multi-agent literature, an agent generally has goals, autonomy, and potentially the capacity to act on an environment [8]. More recent discussion of agentic clinical AI similarly highlights the risks created when systems can access data, use tools, or perform goal-directed tasks [9]. MAGI personas have none of these permissions. They are constrained analytical roles within a single evaluation process. They cannot order tests, access records beyond the submitted case material, communicate with patients, or execute an intervention.
These roles are simulated analytical perspectives, not licensed professionals or independent expert opinions. In a single-model implementation, different prompts do not establish statistical independence or epistemic diversity. Initial role analyses should be generated in isolated contexts before synthesis; subsequent rounds must record what information each role received. Correlated errors, anchoring by the coordinator, and sensitivity to role order or shared context remain hypotheses for empirical assessment.

Table 1.
Analytical roles and safeguards in the MAGI framework.
| Analytical role | Primary question | Required safeguard |
|---|---|---|
| Legal | Which professional, regulatory, consent, confidentiality, and documentation duties apply? | No legal conclusion is treated as jurisdiction-wide advice; unresolved legal questions are escalated to qualified counsel. |
| Personalist bioethics | Does the proposal respect dignity, autonomy, vulnerability, conscience, and the moral limits of intervention? | The report distinguishes this framework from other ethical theories and does not present a sectarian view as universal consensus. |
| Biomedical | What are the plausible benefits, harms, evidence gaps, contraindications, and physiological uncertainties? | The persona may identify uncertainty but cannot substitute for examination, guidelines, or specialist consultation. |
| Coordinator | Where do the roles converge, diverge, or require additional information? | The coordinator summarizes; it does not adjudicate moral truth or issue a clinical order. |
The legal role is grounded in the applicable professional duties of the setting in which MAGI is deployed. In Brazil, the Code of Medical Ethics establishes duties relating to autonomy, informed consent, professional responsibility, confidentiality, and the physician-patient relationship [10]. The role should not be configured as generic legal advice. Its purpose is to flag a need for review when the case contains a regulatory, documentation, consent, or liability issue beyond the system’s scope. Brazil-specific configuration must also account for CFM Resolution No. 2,454/2026 and its rectification [11]. The rule addresses AI governance, human supervision, professional autonomy, documentation, and data protection. MAGI does not itself establish compliance or replace institutional risk classification.
The personalist bioethics role draws on the account of the person as intrinsically worthy and not reducible to an instrument, outcome, or aggregate utility [12]. It should be explicit that this is one ethical framework among several. Principles of respect for autonomy, nonmaleficence, beneficence, and justice provide an additional, widely used vocabulary for examining conflicts in healthcare ethics [13]. The role does not replace institutional ethics consultation, religious counsel, or the patient’s own beliefs; it makes the relevant moral tension visible.
The personalist perspective is retained as an explicit normative commitment, not as a proxy for religious authority. An implementation must record the patient’s expressed values without inferring beliefs from demographic characteristics. Reviewers should be able to request alternative ethical perspectives, including principlist or care-ethics analysis, and preserve unresolved differences. The choice and coverage of ethical perspectives require scrutiny by a plural multidisciplinary group, including patient representation.
The biomedical role is limited to the clinical and evidentiary dimensions stated in the case. It should identify missing information, uncertainty, potential harms, and reasons a recommendation might not generalize to the individual patient. It does not create an evidentiary basis where one is absent. When decisive factual uncertainty remains, the output must state this plainly and require human verification.
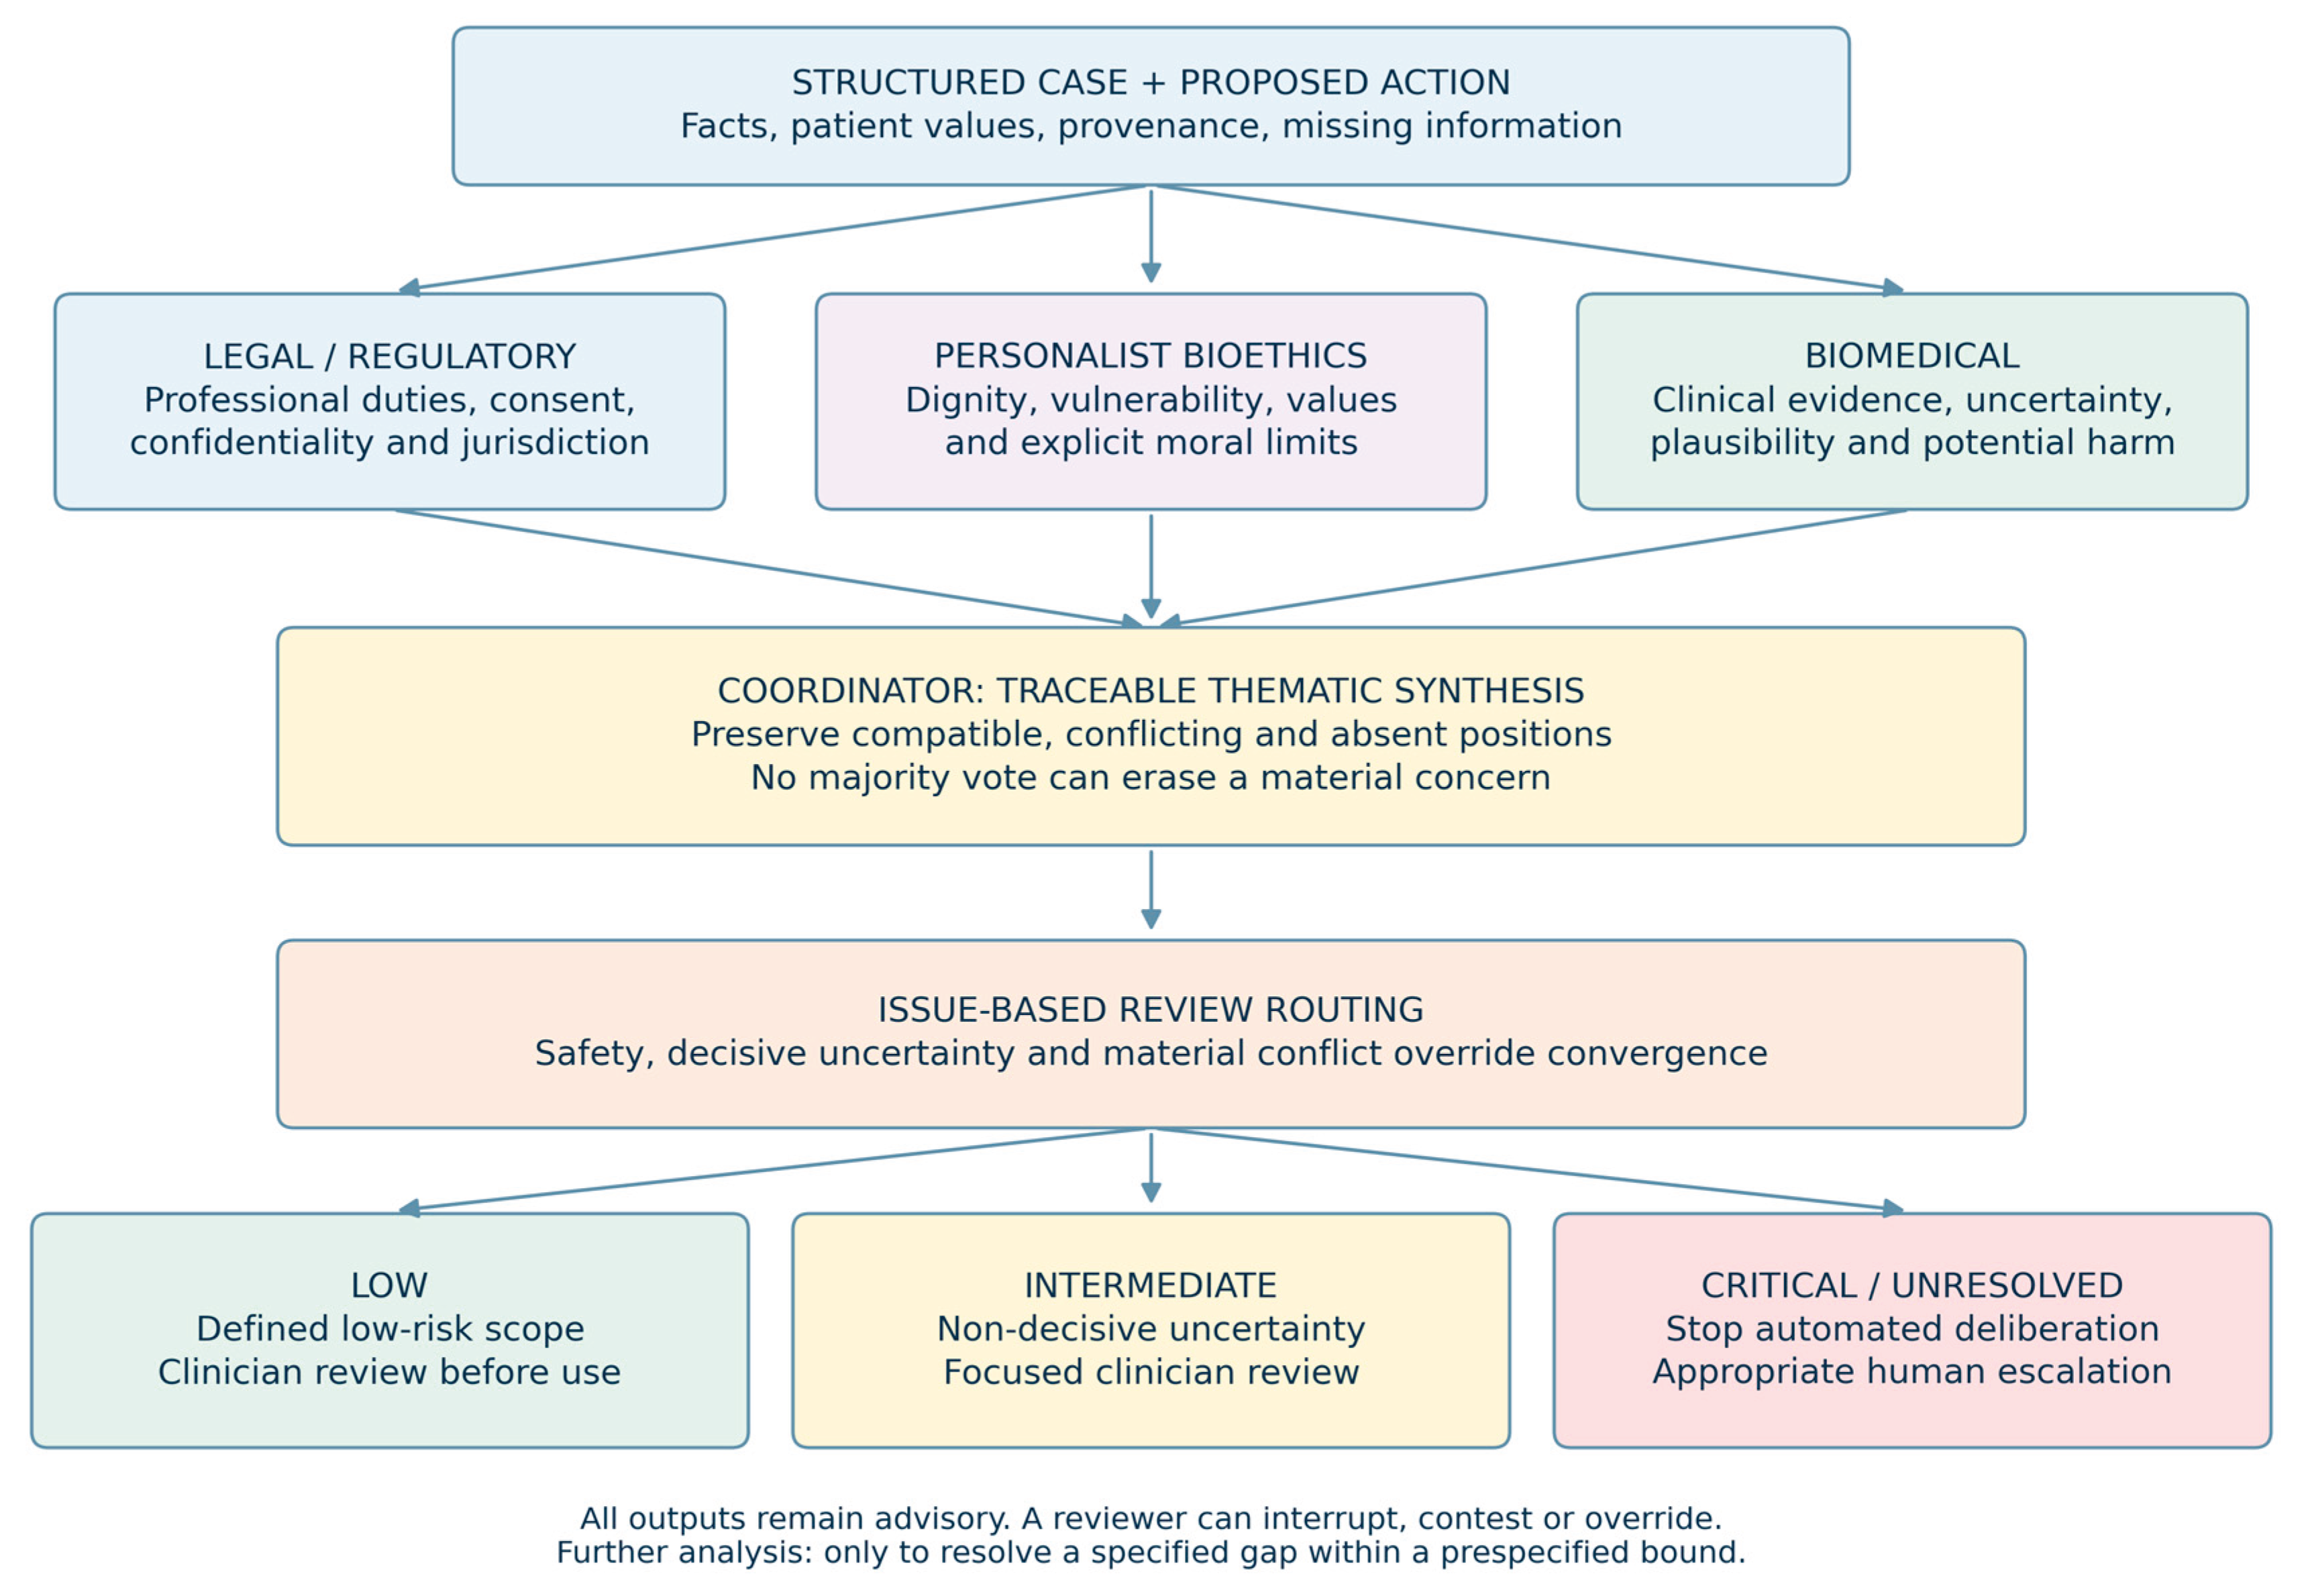
Figure 1.
Proposed MAGI multipersona workflow and human-in-the-loop review. Safety concerns override thematic convergence. All outputs require clinician review; additional analysis is permitted only for a specific, resolvable information gap within a prespecified bound. No numerical threshold or iteration count is validated.
Deliberation and Thematic Synthesis
MAGI proposes a structured thematic synthesis informed by content analysis. Bardin provides a conceptual basis for identifying units of meaning, grouping themes, and interpreting textual convergence and divergence [14]; this citation does not establish a validated automated coding method. Each persona should return a common schema: case facts with provenance, duties or values, potential harms, uncertainty, escalation concerns, and an explicit supporting rationale. The coordinator should produce a theme register, a convergence summary, an unresolved-conflict summary, and a human-review recommendation. Generated rationales are inspectable outputs, not proof of access to the model’s internal reasoning.
For a testable implementation, a unit of analysis should be one distinct case-relevant assertion about a fact, duty, value, harm, or uncertainty. A versioned codebook must define theme boundaries, coding examples, source attribution, and rules for compatible, conflicting, absent, or not-applicable positions. Absence of a concern must not be coded as agreement. A material objection raised by one role must remain visible even when the other roles agree. The theme register should retain links to the relevant role output and case material so that human reviewers can contest the synthesis.
A numerical convergence score is optional and is not a core safety requirement. This proposal does not specify a validated formula, denominator, weighting scheme, or operating threshold. If studied, these choices must be prespecified, distinguish missing analysis from agreement, and be evaluated for coding reliability and association with externally assessed escalation needs. A high score may reflect shared assumptions, incomplete case data, or prompt constraints; a low score may appropriately preserve genuine conflict. Neither a high score nor rapid agreement may override a material safety, consent, legal, or evidentiary concern.
The proposed process has four stages. First, the case is structured around the action under consideration, relevant circumstances, patient preferences, and missing information, without converting the question into a binary ethical verdict. Second, the three roles analyze the case separately. Third, the coordinator identifies thematic overlap, factual gaps, normative conflict, and escalation concerns. Fourth, another round is permitted only when a specific information gap can be addressed within a prospectively defined iteration and time limit. Persistent material conflict, an unresolved decisive gap, or a high-risk feature requires cessation of automated deliberation and human escalation. Rephrasing the same arguments to obtain consensus is not a reason to continue.
Human Review and Criticality Triage
Human review is required at every level before any output is used to inform care. Low criticality denotes a case within a prospectively defined low-risk scope with no identified material unresolved concern; it does not mean the proposed action is safe. Intermediate criticality denotes non-decisive uncertainty or clarified disagreement that warrants focused review of the underlying reasons. Critical status denotes persistent material normative conflict, decisive missing clinical information, substantial risk of irreversible harm, or an unresolved material legal or consent concern. Any such feature takes precedence over convergence. Where the system cannot support a level assignment, it must abstain and request human review rather than default to low criticality. These are proposed case-review categories, not the regulatory risk categories for AI systems [11].
The responsible clinician should verify the classification and select the referral route according to the concern: a relevant specialist for clinical uncertainty, clinical ethics consultation for unresolved value conflict, legal counsel for legal questions, or the appropriate institutional governance, privacy, or patient-safety service. A research ethics committee or IRB has a distinct role in research oversight. No committee is assigned universal authority over clinical decisions. The reviewer must be able to disagree, record the basis for overriding the output, and obtain a second opinion; urgent care must not be delayed while awaiting automated or committee deliberation.
Two proposed interface requirements are motivated by automation-bias evidence, although their effectiveness within MAGI remains untested. First, the report must display the reasons for uncertainty and disagreement before any summary statement. Second, it must never be presented as a final clinical recommendation or a substitute for deliberation. A technically fluent output can increase the risk of misplaced confidence; therefore, the interface should make escalation and uncertainty more salient than apparent consensus [4,5].
The framework also requires an immediate stop mechanism. A human reviewer must be able to interrupt processing, prevent further iterations, preserve the partial audit trail, and transfer the case to an appropriate human process. The interruption record should state that the output is incomplete and must not be used to support a clinical action. Here, human-in-the-loop denotes mandatory review before clinical use; the ability to interrupt processing is an additional safeguard, not evidence of autonomous clinical operation.
Implementation Boundaries and Evaluation Plan
Before clinical deployment, MAGI requires staged prospective evaluation. Initial testing should use standardized synthetic or appropriately de-identified cases with predefined clinical and ethical issues; published clinical-bioethics cases may support development [15], but held-out evaluation cases should be separately curated to reduce memorization and contamination concerns. A multidisciplinary reference panel should include relevant clinicians, ethics expertise, and legal expertise where needed, with patient representation in defining value-sensitive criteria. Panelists should assess cases independently of MAGI outputs before adjudication. The reference should distinguish clear safety or escalation requirements from ethically defensible disagreement; majority opinion is not a gold standard for moral truth.
A prespecified primary safety endpoint should assess the sensitivity for detecting cases requiring escalation, with confidence intervals and severity-weighted review of missed critical concerns. Secondary outcomes should include inappropriate escalation, unsupported factual or legal claims, omitted concerns, reproducibility, panel agreement, and reviewer comprehension. The protocol should define the unit of analysis, case sampling, sample-size or precision rationale, missing or invalid outputs, multiplicity where relevant, and uncertainty estimation that accounts for repeated runs within cases. Performance should be examined across relevant clinical contexts, languages, and patient groups where sample sizes permit. Cases used to tune prompts or thresholds must be separated from final evaluation cases.
A second stage should compare the multipersona workflow with clinician-only review and a single structured-prompt alternative, using the same cases and comparable information and model budgets for the AI conditions. Simulation should assess the quality and speed of issue detection, appropriate reliance, overrides, and escalation burden. Silent deployment, if ethically and institutionally authorized, can assess case coverage and workflow fit but cannot establish behavioral effects when outputs are hidden from clinicians. Any subsequent live early-stage clinical evaluation should be reported using DECIDE-AI where applicable [16]; it is a reporting guideline, not certification of safety. Advancement between stages requires prespecified safety criteria. Coherent narratives alone do not justify patient-care use.
A reproducibility package for any implementation must document the provider, exact model identifier and snapshot when available, access dates, system and role prompts, coordinator instructions, inference parameters exposed by the interface, tool permissions, evidence sources, context-sharing rules, iteration limits, and number of repeated runs. Unsupported parameters must be recorded as unavailable rather than assumed. Evaluation should test prompt injection, invalid outputs, role-order effects, correlated failures, and factual or citation errors. Model or prompt changes should trigger versioning and proportionate re-evaluation. A model-specific prototype, if developed, must be distinguished from the model-agnostic architecture proposed here.
Data governance is equally important. Inputs should be minimized, de-identified whenever possible, access controlled, logged, and retained according to institutional policy. If an implementation uses external language-model services, the institution must assess data transfer, security, contractual controls, and compliance with applicable law. Human reviewers must be able to inspect the case material and generated rationale and evidence summary on which a triage recommendation is based. The proposal follows the broader emphasis on accountability and inclusive governance in WHO guidance [7]. An implementation should assign responsibility for incident review, access control, retention and deletion, version changes, suspension, and re-evaluation; audit logs require the same protection as other sensitive case data. Institutional review must address patient information and preferences, secondary use, and any applicable regulatory classification. The term guardrail does not exempt a system from these obligations.
Discussion
MAGI proposes a case-level deliberative workflow within existing clinical AI governance, rather than claiming that governance or human review is absent from prior work [7]. The framework does not assume that additional model reasoning equals safer care. Instead, it treats clinical AI as a source of potentially useful but fallible analysis that must be located within professional, ethical, and institutional accountability. This orientation is consistent with literature describing the value of AI support alongside the continuing importance of clinical judgment and human relationships [3,6].
The multipersona structure has potential, rather than demonstrated, practical advantages. It separates legal, moral, and biomedical questions that may be conflated in a generic prompt and is intended to preserve disagreement in a reviewable report. Its proposed contribution is the coupling of explicit analytical roles with issue-based escalation, not the invention of human oversight. Whether this arrangement adds value over a well-designed checklist or single structured prompt requires direct comparison. The personas do not constitute a multidisciplinary team, and an audit trail does not establish factual correctness or faithful access to internal model reasoning.
The personalist role deserves particular care. It can enrich deliberation by foregrounding dignity, vulnerability, and the non-instrumental value of the patient. However, clinical institutions serve individuals with diverse convictions. The framework should disclose the ethical perspective used, make room for alternative ethical analysis, and avoid representing a single moral tradition as the patient’s preference or as a binding institutional conclusion.
Limitations
No empirical performance, usability, reliability, or clinical impact estimates are reported. The selection of three roles is not shown to be comprehensive or optimal, and the normative orientation may require adaptation to diverse institutions and patient values. Although its development history is outlined above, it was not documented as a reproducible review or formal consensus process. Thematic synthesis and review levels remain unvalidated design choices. Shared-model biases, erroneous source attribution, missing case information, and coordinator errors may create false reassurance despite apparently diverse outputs. Human review itself can fail through workload, limited expertise, or automation bias. These limitations preclude claims of established safety, effectiveness, or generalizability.
Conclusions
MAGI is a proposed architecture for making ethical conflict, uncertainty, and automation-related risk visible in clinical AI workflows. It is designed to support, not replace, clinicians and institutional ethics processes. Its intended safety function is to flag situations in which automated analysis may be insufficient and direct the case to accountable human review. Validation and applicable institutional authorization should precede clinical use, with particular attention to calibration, failure modes, usability, data governance, and the effect of the framework on appropriate reliance.
Author Contributions
GHYJ conceived the original research programme and drafted the manuscript. LMV critically revised the manuscript. Both authors approved the final version and agree to be accountable for the work.
Funding
No external funding was received for this conceptual work.
Institutional Review Board Statement
Not applicable. This conceptual manuscript reports no research involving human participants, identifiable data, or animals.
Data Availability Statement
This article reports a conceptual specification and presents no empirical dataset or validated implementation. Code for the GPT-5.6-Terra API prototype will be made publicly available at https://github.com/ghyoshinari/magi_debate. Versioned prompts, configuration files, evaluation protocols, and audit schemas will be made available where permitted by privacy, access, and institutional requirements.
Generative AI assistance
GPT-5.6-Terra was accessed via API for prototype implementation. ChatGPT 5.6 was used to assist scientific editing, reference checking, and preparation of the revised workflow figure. These uses do not constitute empirical validation or transfer scientific responsibility from the authors.
Conflicts of Interest
The authors declare no competing interests.
References
- Singhal, K.; Azizi, S.; Tu, T.; Mahdavi, S.S.; Wei, J.; Chung, H.W.; et al. Large language models encode clinical knowledge. Nature 2023, 620(7972), 172–180. [Google Scholar] [CrossRef]
- Rajpurkar, P.; Chen, E.; Banerjee, O.; Topol, E.J. AI in health and medicine. Nat. Med. 2022, 28(1), 31–38. [Google Scholar] [CrossRef]
- Topol, E.J. High-performance medicine: the convergence of human and artificial intelligence. Nat. Med. 2019, 25(1), 44–56. [Google Scholar] [CrossRef]
- Parasuraman, R.; Manzey, D.H. Complacency and bias in human use of automation: an attentional integration. Hum. Factors 2010, 52(3), 381–410. [Google Scholar] [CrossRef]
- Goddard, K.; Roudsari, A.; Wyatt, J.C. Automation bias: a systematic review of frequency, effect mediators, and mitigators. J. Am. Med. Inf. Assoc. 2012, 19(1), 121–127. [Google Scholar] [CrossRef]
- Hindhede, A.L.; Andersen, V.H. The role of AI and personalized medicine in healthcare: balancing technological advancements and the art of medicine. BMC Med. Educ. 2025, 25, 1580. [Google Scholar] [CrossRef]
- World Health Organization. Ethics and governance of artificial intelligence for health: WHO guidance; World Health Organization: Geneva, 2021; Available online: https://www.who.int/publications/i/item/9789240029200ISBN 978-92-4-002920-0.
- Isern, D.; Moreno, A. A systematic literature review of agents applied in healthcare. J. Med. Syst. 2016, 40(2), 43. [Google Scholar] [CrossRef]
- Choi, J.Y.; Yoo, T.K. Transforming clinical medicine with multimodal artificial intelligence, agentic systems, and the model-context protocol: a perspective on future directions. Discov. Health Syst. 2026, 5, 6. [Google Scholar] [CrossRef]
- Conselho Federal de Medicina. Resolução CFM no 2.217, de 27 de setembro de 2018; Aprova o Código de Ética Médica. Diário Oficial da União, 1 Nov 2018; Seção 1, p. 179.
- Conselho Federal de Medicina. Normatiza o uso da inteligência artificial na medicina. Resolução CFM nº 2.454; Diário Oficial da União. 2026; Seção 1:158, p. Seção 1:91. Available online: https://sistemas.cfm.org.br/normas/arquivos/resolucoes/BR/2026/2454_2026.pdf.
- Sgreccia, E. Personalist bioethics: foundations and applications; The National Catholic Bioethics Center: Philadelphia, 2012. [Google Scholar]
- Beauchamp, T.L.; Childress, J.F. Principles of biomedical ethics, 8th ed.; Oxford University Press: New York, 2019. [Google Scholar]
- Bardin, L. Análise de conteúdo; Edições 70: Lisboa, 2011. [Google Scholar]
- Conselho Regional de Medicina do Estado de São Paulo. Bioética clínica: reflexões e discussões sobre casos selecionados, 3a ed.; CREMESP: São Paulo, 2011. [Google Scholar]
- Vasey, B.; Nagendran, M.; Campbell, B.; Clifton, D.A.; Collins, G.S.; Denaxas, S.; et al. Reporting guideline for the early-stage clinical evaluation of decision support systems driven by artificial intelligence: DECIDE-AI. Nat. Med. 2022, 28(5), 924–933. [Google Scholar] [CrossRef]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.