

Submitted:
02 November 2026
Posted:
05 November 2026
You are already at the latest version
Abstract
Cardiovascular diseases (CVD) and osteoporosis pose major clinical challenges for older adults worldwide. Evidence suggests these diseases are interconnected through shared biological mechanisms and risk factors. However, differences in the associations between specific CVD subtypes and osteoporosis remain incompletely understood. We examine osteoporosis in relation to coronary artery disease (CAD) and myocardial infarction (MI), stroke, atrial fibrillation (AF), peripheral arterial disease (PAD), and heart failure (HF). The review considers epidemiological evidence, shared biological mechanisms, medication effects, and questions for future research on cardiovascular–bone interactions. Studies addressing CVD, bone mineral density (BMD), osteoporosis, or fracture outcomes were identified through PubMed and backward citation searching.Across these cardiovascular conditions, studies report associations with low BMD, osteoporosis, or hip fracture. Their magnitude and consistency vary, however, according to the CVD subtype, study population, and skeletal outcome. Proposed links include chronic inflammation, oxidative stress, vascular calcification, endocrine dysregulation, and changes in RANK/RANKL/OPG and Wnt/β-catenin signaling. Genomic approach, large population-based cohorts, and causal inference methods offer opportunities to improve understanding of the complex cardiovascular-bone interactions. Further research is needed to classify subtype-specific associations and mechanisms, assess potential causal relationships, and determine whether these insights can improve risk prediction, prevention, early detection, and management of CVDs, osteoporosis, and osteoporotic hip fractures.
Keywords:
cardiovascular disease
; osteoporosis
; bone mineral density
; hip fracture
; cardiovascular–bone interactions
; vascular calcification
1. Introduction
Cardiovascular diseases (CVDs) contribute substantially to global morbidity and mortality and are a public health concern [1]. CVDs are associated with multiple risk factors, including age, sex, genetic susceptibility, smoking, obesity, dyslipidemia, hypertension, diabetes, and behavioral factors [2,3]. Osteoporosis is a common systemic skeletal disease marked by reduced bone mass, deterioration of bone microarchitecture, and increased bone fragility [4,5]. Bone mineral density (BMD) measured by dual-energy X-ray absorptiometry (DXA) at the hip or lumbar spine is commonly used to support its diagnosis [6,7].
CVDs and osteoporosis frequently occur in the same patients. It is still uncertain whether their association mainly reflects shared risk factors or whether either condition contributes to the other [8]. Reports linking CVDs with lower BMD provide evidence of their coexistence [9,10,11]. For example, patients with chronic heart failure (HF) have been reported to have lower BMD than those without HF [10]. Lower BMD has also been associated with a higher subsequent incidence of coronary artery disease and cerebrovascular disease [11,12]. Studies have additionally reported an elevated risk of hip fracture following HF, stroke, or ischemic heart disease [13,14,15]. Furthermore, some deaths following severe osteoporotic fractures have been linked to cardiovascular decompensation [16]. As the population ages, the coexistence of CVDs and osteoporosis is likely to become increasingly common.
Although associations between osteoporosis and individual cardiovascular conditions have been investigated, evidence has rarely been synthesized comparatively across CVD subtypes, and differences in the strength, direction, and underlying mechanisms of these associations remain incompletely understood. Clarifying how CVD subtypes and osteoporosis mutually influence a patient’s clinical condition is therefore important. There is a need for clinicians to use an integrated approach to improve early diagnosis and treatment initiation and prognosis.
The aim of this paper is to synthesize current evidence regarding the relationship between CVD subtypes and osteoporosis, analyze epidemiological findings within the vascular-bone axis, identify CVD subtypes strongly associated with osteoporosis, evaluate shared pathophysiological, biological, and genetic mechanisms, and highlight opportunities for precision medicine, risk prediction, identifying potential therapeutic targets, and future research. We focus on coronary artery disease (CAD) and myocardial infarction (MI), stroke, atrial fibrillation (AF), peripheral arterial disease (PAD), and HF. Comparing evidence across these subtypes may clarify cardiovascular–bone interactions and identify findings relevant to risk prediction, precision medicine, and potential therapeutic targets. It may also show where further research is most needed.
2. Literature Search Strategy
We searched PubMed from June through August 2026 for relevant publications dated 2001–2026 and checked the reference lists of selected articles for additional studies. Search terms addressed osteoporosis, BMD, and hip fracture; CVD, CAD, MI, AF, and stroke; and vascular calcification, RANK/RANKL/OPG, Wnt/β-catenin, and genome-wide association studies. We considered original research articles, systematic reviews, and meta-analyses published in English. Priority was given to studies connecting cardiovascular and skeletal outcomes or examining shared mechanisms, genetics, or medication effects. We excluded articles confined to only one of the two disease areas, non-peer-reviewed work, conference abstracts, and opinion papers without substantive review content.
3. Epidemiological and Clinical Evidence
Earlier research has linked osteoporosis or low BMD to CVD [17]. In a retrospective study of 101 postmenopausal women residing in a nursing home, atherosclerotic vascular disease, including CAD, cerebrovascular disease, or PAD, was present in approximately 61% of women with low BMD compared with 38% of those with normal BMD (p<0.025) [18]. Using National Health and Nutrition Examination Survey data, Yang and Huang reported higher odds of prevalent CVD among participants with osteoporosis (adjusted OR: 3.05, 95% CI: 1.68–5.52) [7]. Their analysis accounted for potential confounders including age, gender, race, smoking status, body mass index, waist circumference, systolic and diastolic blood pressure, hypertension, hyperlipidemia, diabetes mellitus, chronic kidney disease, liver disease, alanine aminotransferase, albumin, aspartate aminotransferase, blood urea nitrogen, creatinine, phosphorus, calcium, high-density lipoprotein cholesterol, total cholesterol, glycated hemoglobin, and vitamin D.
Longitudinal evidence has also linked osteoporosis to subsequent cardiovascular events. In a post hoc analysis of 2,576 postmenopausal women assigned to placebo in the Multiple Outcomes of Raloxifene Evaluation (MORE) trial, Tankó et al. reported that women with osteoporosis had 3.9 times the risk of cardiovascular events over four years compared with women with low bone mass and no vertebral fractures, after accounting for cardiovascular risk factors with a composite score that included age, diabetes mellitus, current smoking, hypertension, hyperlipidemia, and established coronary disease (HR: 3.9, 95% CI: 2.0–7.7) [19]. Cardiovascular event risk also increased with the number and severity of vertebral fractures present at baseline [19]. Similarly, Veronese et al. pooled adjusted estimates from 11 studies and observed higher incident CVD risk among individuals with low BMD (HR: 1.33, 95% CI: 1.27–1.38; I² = 53%) [11]. For incident CVD, Veronese et al. pooled adjusted estimates from 11 studies and reported an association with low BMD (HR: 1.33, 95% CI: 1.27–1.38; I² = 53%) [11]. Park et al. examined 12,681 women aged 50 years or older in a retrospective study. Osteoporosis was independently associated with subsequent atherosclerotic cardiovascular disease events in that population (adjusted HR: 1.79, p < 0.001) [20].
Associations have also been reported between CVD and fracture outcomes. In an analysis of hospital discharge records for older inpatients in Beijing, Xu et al. found that hip fracture occurred more often among patients with CVD than among those without CVD after adjustment for age, gender, and the number of comorbidities (adjusted rate ratio: 1.53, 95% CI: 1.47–1.60) [21]. Evidence of a temporal association was provided by Sennerby et al. in a population-based cohort of Swedish twins. Compared with individuals without CVD, the adjusted HRs for subsequent hip fracture were 4.40 (95% CI: 3.43–5.63) after HF, 5.09 (95% CI: 4.18–6.20) after stroke, 2.32 (95% CI: 1.91–2.84) after ischemic heart disease, and 3.20 (95% CI: 2.28–4.50) after peripheral atherosclerosis [15]. These observational findings support associations in both temporal directions but do not establish a causal relationship.
3.1. CAD/CHD and Osteoporosis
CAD, also commonly referred to as coronary heart disease (CHD), is characterized mainly by atherosclerotic plaques in the coronary arteries that narrow the vessel lumen and restrict myocardial blood supply [22,23]. Marcovitz et al. studied 209 patients who had undergone both DXA and coronary angiography. After adjustment for other risk factors, osteoporosis was associated with greater odds of significant CAD, defined as at least 50% narrowing of a major coronary artery (OR: 5.6, 95% CI: 2.6–12.0) [24]. In a meta-analysis of three longitudinal studies, Veronese et al. found that low BMD was associated with incident CHD, although heterogeneity was substantial (HR: 1.31, 95% CI: 1.25–1.38; I² = 82%) [11].
Studies have also examined whether BMD relates to myocardial function and later cardiac events. Fiechter et al. assessed vertebral BMD using CT in 491 patients undergoing positron emission tomography/CT for CAD evaluation. Reduced BMD was associated with major adverse cardiac events (MACE) in a fully adjusted proportional hazards regression model (p = 0.015), and a sex-by BMD interaction was detected (p = 0.007) [25]. Among men, those with abnormal myocardial perfusion or impaired left ventricular ejection fraction had lower BMD; this pattern was not observed in women, suggesting potential sex differences in these associations [25]. Findings concerning fracture outcomes also varied by cardiovascular subtype. Although Xu et al. reported an association between overall CVD and hip fracture, ischemic heart disease was not significantly associated with hip fracture in the overall study population (adjusted rate ratio: 1.05, 95% CI: 1.00–1.11; p = 0.062) [21]. Overall, these studies suggest associations between low BMD or osteoporosis and CAD-related outcomes, although their observational designs limit causal inference [11,16,24,25].
3.2. Stroke and Osteoporosis
Stroke results from vascular injury to the central nervous system and causes acute neurological dysfunction; it is a major cause of long-term disability in adults [26,27,28]. Associations between stroke and low BMD have been reported. Jørgensen et al. found that femoral neck BMD was 8% lower among women with acute stroke than among control participants (p = 0.007) [29]. Bone loss has also been assessed over time after stroke. In a meta-analysis and systematic review by Wang et al., eight studies involving 369 participants showed a decline in paretic-side femoral neck BMD from baseline to follow-up (mean difference: −0.07 g/cm², 95% CI: −0.09 to −0.04), whereas the pooled analysis of lumbar spine BMD showed no significant change [30].
Fracture outcome have also been investigated after stroke [31]. In a study of 131 adults aged ≥50 years with ischemic stroke, Liu et al. reported that 11 participants (8.4%) experienced a minimal-trauma fracture within 12 months after stroke [31]. In a population-based retrospective cohort, Lee et al. reported a higher subsequent hip fracture risk in stroke survivors than in matched controls (adjusted HR: 2.42, 95% CI: 2.30–2.55) [32]. Risk was greatest among survivors with severe post-stroke disability. This result should be considered alongside studies using different populations and skeletal outcomes. The meta-analysis by Wang et al. found the pooled association between stroke and subsequent osteoporosis or osteoporotic fractures was not statistical significance (three studies; HR: 1.43, 95% CI: 0.95–2.13), with substantial heterogeneity (I² = 97%) [30]. Evidence of post-stroke BMD loss should be distinguished from evidence concerning osteoporosis diagnoses and fracture incidence.
3.3. AF and Osteoporosis
AF is a common sustained cardiac arrhythmia [33] characterized by disorganized atrial electrical activity and ineffective atrial contraction [34]. Several observational studies have examined its association with fracture risk. In a study of 113,600 people, Wong et al. found that AF was associated with a higher adjusted hazard of subsequent hip fracture in both men (HR: 1.97, 95% CI: 1.61–2.42) and women (HR: 2.08, 95% CI: 1.80–2.39) [13]. Kim et al. studied 31,778 patients with osteoporosis and reported a smaller association between coexisting AF and fracture during a median follow-up of 48 months (adjusted HR: 1.21, 95% CI: 1.02–1.41) [35]. Results were not uniform across studies: among 4,462 older adults in the Cardiovascular Health Study, Wallace et al. found no statistically significant association between incident AF and later hip fracture (adjusted HR: 1.09, 95% CI: 0.83–1.42) [36].
Yu et al. examined the relationship in the other direction. In the UK Biobank cohort, participants with osteoporosis had a higher incidence of AF after multivariable adjustment (HR: 1.24, 95% CI: 1.14–1.35) [33]. The other cohorts in their study did not define exposure and outcome identically: the Framingham Offspring Study used the lowest 5% of BMD to represent severe bone mineral loss, while the Health and Retirement Study recorded abnormal heart rhythm rather than specifically confirmed AF [33]. These differences matter when comparing the findings across cohorts and interpreting the association between AF and skeletal health.
3.4. PAD and Osteoporosis
In PAD, atherosclerotic narrowing or occlusion affects peripheral arteries, most often those supplying the legs [37,38]. Walking limitations and reduced muscle strength are common concerns, and impaired mobility may contribute to falls in older adults [38]. In the Rancho Bernardo Study, von Mühlen et al. found women with PAD had a higher prevalence of osteoporosis among women without PAD (p < 0.05) and experienced greater hip bone loss over an average four-year follow-up (p = 0.05) [39]. However, these associations lost statistical significance when age was accounted for. PAD was not associated with osteoporosis in men, and no significant association with osteoporotic fractures was observed in either sex [39].
Ungprasert et al. combined studies of PAD and incident hip fracture and reported a pooled rate ratio of 1.64 (95% CI: 1.17–2.29), with substantial heterogeneity (I² = 80%) [38]. The association remained statistically significant when prospective studies (rate ratio: 1.60, 95% CI: 1.12–2.28; I² = 0%) and retrospective studies (rate ratio: 1.72, 95% CI: 1.07–2.77; I² = 92%) were analyzed separately [38]. Evidence has also been reported in the opposite temporal direction. In a Taiwanese population-based longitudinal study, Syu et al. found a higher incidence of PAD among people with osteoporosis than among those without it after adjustment for potential confounders (HR: 1.18, 95% CI: 1.08–1.29) [40].
3.5. HF and Osteoporosis
HF occurs when cardiac structural or functional abnormalities impair ventricular filling or ejection and produce characteristic symptoms and signs [41]. Xing et al. combined six studies comparing BMD in people with and without chronic HF [10]. The HF groups had lower whole-body and femoral neck BMD, while lumbar spine BMD did not differ significantly. In subgroup analyses, BMD deficits appeared larger with greater HF severity [10].
Osteoporosis has also been examined as a prognostic marker among patients already living with HF. In a retrospective study of 303 patients with chronic HF, Katano et al. found that osteoporosis at two or three measured skeletal sites was associated with more frequent occurrence of the composite outcome of death or unplanned readmission for worsening HF or arrhythmia, after adjustment for age, sex, and NT-proBNP (HR 2.21, 95% CI 1.10–4.43) [42]. However, the association was not statistically significant after the same adjustment when osteoporosis was classified simply as present or absent [42]. Osteoporosis at multiple skeletal sites was also independently associated with a lower appendicular skeletal muscle mass index [42].
4. Biological and Pathophysiological Mechanisms Between Osteoporosis and Cardiovascular Disease
4.1. Shared Risk Factors
Cardiovascular disease and osteoporosis share several demographic, lifestyle, and clinical risk factors that may contribute to their frequent coexistence, particularly in older populations. These include aging, smoking, physical inactivity, excessive alcohol consumption, menopausal status, and selected cardiometabolic conditions such as hypertension and obesity [2,12,17]. However, the direction and magnitude of these associations may differ between cardiovascular and skeletal outcomes; for example, higher body weight is a recognized cardiovascular risk factor but may not confer the same risk for low BMD. Shared pathophysiology is highlighted by shared risk factors that may concurrently promote or inhibit atherosclerosis and bone demineralization [2,9,12,17]. These risk factors can help explain the association between the two diseases [2,12,17]. Furthermore, the clustering of shared risk factors may therefore partly account for the epidemiological association between cardiovascular disease and osteoporosis (Figure 1).
4.2. Biological Mechanisms
The common pathophysiological mechanisms include inflammatory cytokines, oxidized lipids, sex hormones, vitamin K deficiency, and vitamin D, which play a role in the progression of CVD and osteoporosis [2]. Oxidative stress, inflammation, free radicals, and lipid metabolism are involved in both bone and cardiovascular health [9] (Figure 2 and Table 1).
4.2.1. Inflammatory Markers and Oxidative Stress
Inflammatory Markers
Inflammation plays a pivotal role in the stages of atherogenesis as well as in bone loss. Inflammatory diseases such as lupus, rheumatoid arthritis, and Crohn’s disease have an increased risk of osteoporosis and fractures. Systemic inflammatory processes influence osteoporosis through cytokines, including IL-6 and TNF-α. Increased levels of inflammatory cytokines such as IL-6 and TNF-α are associated with aging. IL-6 stimulates osteoclasts, increasing bone remodeling and bone loss. It is also used as a marker of subclinical CVD in older adults [2]. TNF-α stimulates bone resorption and inhibits bone formation. Individuals with high inflammatory marker have been found to have increased risk of fracture [43] and cardiovascular events [2].
Oxidative stress
Studies have shown that oxidative stress is the common mechanism associated with vascular remodelling and endothelial dysfunction [44], while also affecting bone formation through stimulation of osteoclast activity while suppressing osteoblast differentiation. Oxidative stress promotes osteoclastogenesis and blocks osteoblast function in bone metabolism [45,46]. Inflammatory cytokines and ROS activate NF-κB, a transcription factor that induces RANKL expression; RANKL then binds to RANK on the osteoclast precursor, promoting osteoclast differentiation and activation. This increases bone resorption and contributes to osteoporosis pathogenesi [44]. ROS influences endothelial dysfunction, vascular remodeling, and inflammation in hypertension. Nitric oxide bioavailability is reduced and smooth muscle cell proliferation is promoted by ROS, therefore contributing to hypertension development [47]. Similar redox-sensitive pathways like NF-κB are upregulated in osteoporosis and increased inflammation and vascular injury. Oxidative stress is a shared mechanism between hypertension and osteoporosis, and this can have an effect on therapies used to target redox-pathways [44,48].
4.2.2. Lipid Metabolism and Oxidative Modification
The lipo-oxidizing 12/15-lipoxygenase system is another proposed biological link between CVD and osteoporosis [14]. Oxidized lipids play a role in atherogenesis and may help explain the coexistence of bone loss and vascular calcification. The effects of oxidized lipids differ between vascular and skeletal cells. In vascular calcifying cells, they favor osteoblast-like differentiation and increase alkaline phosphatase (ALP) activity; in bone, they can interfere with osteoblast development and are associated with lower BMD [42,49]. These lipids may therefore promote both atherogenesis and vascular mineralization while limiting new bone formation [19]. Oxidized low-density lipoprotein (LDL) can also induce signals that favor osteoclast differentiation and prevent stromal cells from completing their differentiation into osteoblasts. Their accumulation in arterial tissue and in vessels supplying bone offers another possible connection between vascular calcification and impaired skeletal mineralization. Osteoporosis in postmenopausal women is associated with higher LDL cholesterol and lower HDL cholesterol levels [49].
4.2.3. Mineral Metabolism and Endocrine Dysregulation
Vitamin D & Calcium
Vitamin D contributes to calcium homeostasis and the mineralization of bone [42]. Lower vitamin D status has been associated with lower BMD and greater susceptibility to falls and fractures. Its possible cardiovascular relevance includes vascular calcification and changes in the renin–angiotensin system. Activation of this system has been proposed as one route connecting vitamin D deficiency with hypertension, left ventricular hypertrophy, and coronary artery calcification [50]. Lower circulating vitamin D levels have also been described in patients with chronic HF [42]. Calcium absorption is reduced in vitamin D deficiency, causing low serum calcium, hypersecretion of calcitriol, and the parathyroid hormone. This results in the mobilization of calcium and phosphorus from the bones to maintain optimal levels of calcium and phosphorus for bone turnover and metabolic processes [50]. On the other hand, calcium deposition leads to increased arterial stiffness and pulse wave velocity. Calcification reduces the elasticity of vessels and adversely affects the hemodynamic parameters of the cardiovascular system, resulting in clinical and sub-clinical cardiovascular events [11].
Vitamin K
Vitamin K is involved in the γ-carboxylation of proteins important to bone and vascular mineralization, including matrix Gla protein (MGP) [50]. Lower dietary intake or circulating levels of vitamin K have been associated with reduced BMD and a higher risk of hip fracture. When vitamin K is insufficient, more MGP remains uncarboxylated and may be less effective at restraining mineral deposition in vessels. This mechanism has been proposed to connect low vitamin K status with arterial calcification and coronary heart disease. Observational findings have also linked higher vitamin K intake to slower progression of vascular calcification and greater arterial elasticity [49,50]. Higher concentrations of uncarboxylated MGP have also been linked to cardiovascular calcification and mortality [49]. Thus, vitamin K status may be relevant when interpreting the coexistence of skeletal and cardiovascular abnormalities [50].
Phosphate
Phosphate is a structural component of bone and is required for normal mineralization. Inadequate phosphate availability can impair bone formation, whereas excess phosphate may favor mineral deposition outside the skeleton. In vascular tissue, elevated phosphate can promote calcium–phosphate deposition and calcification; the extent of mineralization also depends on the balance between phosphate and inhibitors such as pyrophosphate. These processes are particularly relevant in chronic kidney disease (CKD), where disturbances in serum phosphate and PTH commonly occur alongside increased cardiovascular mortality [49].
Hormones (Estrogen)
In bone, estrogen promotes osteoclast apoptosis and stimulates osteoblasts to express osteoprotegerin (OPG) [51]. Its effects on inflammatory signaling, including IL-1, IL-6, and TNF-α, may also be relevant to cardiovascular disease. With estrogen deficiency, cytokine activity may increase while OPG expression and nitric oxide availability decline; these changes can favor bone resorption, vascular inflammation, and atherogenesis [15]. The fall in estrogen levels after menopause therefore contributes substantially to bone loss in women and may also be relevant to their cardiovascular risk [16].
Parathyroid hormone (PTH)
PTH has different effects on bone depending on its exposure pattern. Persistently elevated PTH favors resorption, while intermittent exposure can stimulate bone formation. After PTH binds its receptor on osteoblasts, intracellular signaling engages factors such as cyclic AMP-responsive element-binding protein and RUNX2. PTH can also increase MGP expression during bone formation. In vascular cells, PTH-related protein kinase A (PKA) signaling has been linked to osteogenic differentiation and mineralization. Thus, PTH participates in both skeletal and vascular processes, but its effects depend on the tissue and duration of exposure [49].
4.2.4. Renin-Angiotensin-Aldosterone System (RAAS)
The renin-angiotensin-aldosterone system (RAAS) maintains blood pressure and fluid balance and may also influence bone remodeling. Altered RAAS activity has been discussed as a possible contributor to bone loss associated with estrogen deficiency [46]. Angiotensin II (Ang II) can inhibit osteoblast maturation through the angiotensin II type 1 receptor (AT1R). It may also favor osteoclast activity by increasing receptor activator of nuclear factor κB ligand (RANKL) relative to osteoprotegerin (OPG) [52,53]. Ang II stimulates aldosterone production; mineralocorticoid receptors on osteoclasts, osteocytes, and osteoblasts provide a route through which aldosterone may affect bone turnover. These actions could contribute to changes in BMD and bone microarchitecture. In cardiovascular tissues, Ang II/AT1R signaling is implicated in cardiac remodeling and atherosclerosis [46]. Ang II can also enhance oxidative stress and NF-κB activity, processes relevant to reduced osteoblast differentiation, increased osteoclastogenesis, and vascular injury [44]. RAAS therefore represents a possible shared pathway linking vascular remodeling with bone loss, although the clinical direction of that relationship requires further study.
4.2.5. Vascular Calcification and Bone Mineralization
Vascular calcification is a major complication of CVD and has been associated with myocardial infarction and cardiovascular mortality [51]. Bone mineralization and vascular calcification are highly organized processes that share common pathophysiological and anatomical features with arterial tissue calcification / absorption of calcium and phosphate, sharing similar mechanisms with bone mineralization [54]. Increased bone resorption and abnormal bone modeling cause excess release of calcium from the bone mass, resulting in hypercalcemia, with an increase in calcium ions being associated with increased risk of CVD [9]. Increased bone resorption and abnormal bone modeling cause excess release of calcium from the bone mass, resulting in hypercalcemia; higher calcium ions concentrations have been associated with greater CVD risk [9]. Coronary calcium deposition may alter plaque characteristics as well as the vessels’ ability to respond to changes in blood flow. As calcification progresses, arteries become less compliant, a change associated with hypertension, cardiac hypertrophy, myocardial infarction, and aortic stenosis [49].
The mineral deposited in calcified atherosclerotic plaques resembles the hydroxyapatite found in bone. Such plaques may contain bone-associated proteins, including type I collagen, matrix Gla protein, osteocalcin, BMP-2 and BMP-4, osteonectin, osteopontin, and bone sialoprotein [2]. BMPs, osteopontin, alkaline phosphatase (ALP), and MGP participate in the regulation of mineral deposition. Vascular smooth muscle cells (VSMCs) may adopt an osteoblast-like phenotype and produce mineralized nodules. BMP-2 and BMP-4 can stimulate these cells to express markers of osteogenic activity, including ALP, type I collagen, and osteocalcin [17]. Calcified lesions may also contain cells resembling chondrocytes or osteoclasts, together with hematopoietic bone marrow cells [2]. RANKL and oxidative stress are additional proposed influences on VSMC transformation [17]. The presence of these cells and proteins points to parallels with bone mineralization, although vascular calcification occurs in a different tissue and has different clinical effects.
4.2.6. Bone–Vascular Signaling Pathways
OPG/RANK/RANKL pathway
Bone resorption depends in part on OPG/RANK/RANKL signaling, a pathway also studied in relation to vascular calcification [2]. RANKL is expressed by osteoblasts and stromal cells. By binding to RANK, it promotes the differentiation of monocyte–macrophage precursors into osteoclasts and enhances the activity of mature osteoclasts. Downstream of RANK, Src kinase and TNF receptor-associated factor 6 (TRAF6) contribute to activation of NF-κB and nuclear factor of activated T cells 1 (NFATc1). These factors regulate the gene expression needed for osteoclast differentiation [55]. RANKL signaling can also raise reactive oxygen species (ROS) production, which participates in osteoclastogenesis [49].
Osteoprotegerin binds RANKL and limits its interaction with RANK, thereby inhibiting osteoclast differentiation and bone resorption. OPG has additionally been reported to affect cathepsin K and tissue inhibitor of metalloproteinases-1 (TIMP-1), both of which are relevant to osteoclast activity [49]. Estrogen can increase OPG expression, providing another connection between hormonal changes and bone turnover [56] and is associated with vascular calcification, arterial stiffness, severity of CHD, stroke, and atherosclerosis as well as cardiovascular morbidity and mortality [49]. Additionally, it is released from vascular smooth muscle cells in response to inflammatory stimuli, therefore having a protective role in decreasing vascular inflammation and atherosclerosis [12]. OPG regulates bone resorption through prevention of osteoclast (bone resorption cells) formation and survival via inhibition of RANKL [12]. In the CLARICOR trial, OPG levels were measured in patients with CAD, who were followed for up to 2.6 years for cardiovascular events and 6 years for all-cause mortality. OPG concentrations were significantly greater among non-survivors than survivors and were a strong predictor of all-cause mortality. OPG was also an independent predictor of mortality after adjusting for conventional and clinical cardiovascular risk markers [57]. Serum OPG is a useful predictive marker to assess the risk of bone and CV disease in patients [12]. The study by Katano et al, [42] found that the serum level of RANKL was upregulated in mild HF patients [42]. The OPG/RANK/RANKL triad plays a role in both the bone and cardiovascular system, contributing to calcification of arteries and cardiovascular mortality. However, there is a need to understand their relationship with cardiovascular disease subtypes.
BMP Signalling
BMPs play an important role in osteoblast differentiation and increase collagen synthesis [17,49]. They inhibit osteoblast expression of collagenase 3, which reduces collagen degradation and maintenance of bone mass [49] and also play a mediatory role in vascular calcification. This is evidenced in atheromatous plaques, where the endothelial cells, foam cells, and smooth muscle cells show higher BMP-2 and BMP-4 expression [17]. Osteoblastic differentiation is induced by BMP -2 through induction of the transcription factor Msx2. In arteries, BMP activity has been linked to inflammatory and oxidative responses. Proinflammatory stimuli such as TNF can regulate BMP-2 expression in vascular endothelial and smooth muscle cells. BMP-6 has also been reported to mediate glucocorticoid-stimulated differentiation of osteoblastic cells [49].
Matrix Gla protein (MGP) restrains mineral deposition and can limit BMP-2 binding to its receptor. Osteopontin (OPN) is an extracellular-matrix glycoprotein in bone that binds hydroxyapatite and calcium. OPN is found in bone tissue as well as in atherosclerotic arteries, while elevated levels are associated with vascular calcification [17]. ALP is a marker of bone turnover and often found on the osteoblast surface and catalyzes the hydrolysis of esters. ALP levels are increased in smooth muscles by inflammation and oxidative stress, which is associated with increased mineralization [17].
Wnt-β-catenin signaling pathway
Wnt/β-catenin signaling helps maintain bone by supporting osteoblast formation and limiting excessive resorption. When pathway activity falls, osteoblastogenesis is impaired and bone mass and microarchitecture may deteriorate [58,59]. Wnt signaling activates OPG, which is a decoy receptor to RANKL [58]. By binding to RANKL, OPG prevents its interaction with RANK and reduces osteoclast-mediated bone resorption [58,60]. Malfunctioning of the Wnt pathway is associated with cardiac disease, including myocardial infarction, HF, arrhythmias, and atherosclerosis. In atherosclerosis, it is involved in lipid deposition, cell proliferation, and cell migration [61].
4.2.7. Genetic Association Between CVDs and Osteoporosis
Factors that may partly explain the association between CVDs and hip fracture include telomere shortening, as a marker of biological aging, as well as shared genetic mechanisms involving vascular and skeletal pathways [62]; CVD telomere meta-analysis [15,63]. Genetic factors play an important role in the development of both CVD and osteoporosis, and polymorphisms in genes regulating bone, lipid metabolism, and inflammatory responses and pathways are common risk factors [64].
Genome-wide association studies (GWAS) have provided strong evidence of the genetic component of osteoporosis through the identification of genes involved in the RANK/RANKL/OPG axis and Wnt/Wnt-β-catenin signaling pathways [54,65].
Research involving twins and families has shown that genetic inheritance explains nearly 50–85% of the observed variation in BMD [65]. In a study of identical twin siblings, hip fracture occurred at approximately four times the rate in twins whose co-twin had HF compared with twins without CVD; the rate was approximately doubled when a co-twin had experienced stroke. Co-twin analysis showed that genes influence the development of CVD and fractures [15].
5. Potential Mechanisms Linking CVD Subtypes to Osteoporosis
5.1. Ischemic Heart Disease/CAD and Osteoporosis
Atherosclerotic plaques accumulate within coronary arteries and contain cholesterol, calcium, macrophages, and fibrous connective tissue [3]. It is associated with adverse effects on the cardiovascular system [22]. Disruption of pathways involved in bone-cell stimulation may also contribute to atheromatous plaque development in CAD. Osteoblast-like calcifying vascular cells found in atheroma plaques are phenotypically similar to osteoblasts in bone tissue. Bone tissue proteins like BMP-2, osteopontin, osteoprotegerin, and Gla protein have been found in atheroma plaques [16]. The osteoblast-like calcifying vascular cells are regulated by the same factors as osteoblasts. For example, elevation of osteoprotegerin is associated with CAD [16] and low volumetric BMD is associated with increased morbidity and mortality due to ischemic heart disease [54]. It inhibits the RANK-RANKL pathway, which is responsible for osteoclast stimulation; therefore, it acts as an autocrine and paracrine regulator of vascular calcification, which is the main marker of vascular disease [16].
5.2. Stroke and Osteoporosis
There is a complex interplay between stroke and osteoporosis as they share risk factors, pathophysiological pathways, and genetic factors [66]. Stroke survivors are at high fall risk, which results in increased fracture risk depending on stroke type [32,67] which includes ischemic stroke, small vessel stroke, large artery atherosclerosis stroke and cardioembolic stroke [68]. The reduction in BMD observed in paralyzed limbs compared to the non-paralysed limb following stroke may highlight the combined effects of reduced mobility and increased inflammation. Following stroke, reduced mobility and muscle weakness can shift bone remodeling toward resorption and contribute to rapid bone loss. Post-stroke inflammation may add to this process: cytokines such as interleukin-1 (IL-1) and tumor necrosis factor alpha (TNF-α) can stimulate osteoclast formation while suppressing osteoblast activity [66]. In an experimental study of ischemic stroke in rats, bone marrow cells from paretic limbs showed greater osteoclast formation and bone-resorbing activity in vitro [69].
5.3. AF and Osteoporosis
Osteoporosis has been associated with an increased incidence of AF [33]. A higher risk of AF has also been reported in association with coronary artery calcification [70]. The RANK/RANKL/OPG and Wnt/β-catenin signaling pathways have been proposed as links between bone loss and vascular calcification, although their contribution to the association between osteoporosis and AF remains uncertain [33]. The use of warfarin for stroke prevention in AF may represent another potential link with skeletal fragility because its vitamin K antagonism can interfere with the activation of bone matrix proteins [71]. Wong et al. [13] reported that individuals with a history of AF had approximately twice the hazard of hip fracture compared with those without AF. Although women with AF had a higher absolute risk of hip fracture than men with AF, the relative association between AF and hip fracture was similar in both sexes [13]. Kim et al. also found that, among patients with osteoporosis, cumulative fracture incidence was higher in those with AF than in those without AF (log-rank P < 0.001) [35].
5.4. PAD and Osteoporosis
Several factors could link PAD with poor skeletal health. Reduced blood flow to the hip and lower limbs has been proposed to disturb local bone homeostasis, although its contribution to bone loss is uncertain [72]. PAD may also limit walking and other weight-bearing activities. Along with muscle dysfunction and impaired balance, these limitations could increase the likelihood of falls [72,73]. Shared risk factors, comorbidities, and inflammation may further contribute to the coexistence of PAD and skeletal impairment [72].
5.5. HF and Osteoporosis
HF and osteoporosis commonly occur together in patients over 50 years of age [54] Osteoporosis and HF share numerous pathological mechanisms, and either condition may influence the development of the other [54]. HF patients are prone to develop osteoporosis and fractures [74]; potential contributors include low vitamin D levels, alteration of RAAS, high PTH, low testosterone levels, and metabolic effects of medications [54,75]. In patients with osteoporosis, vitamin D deficiency, elevated plasma PTH levels, and increased Fibroblast Growth Factor 23 (FGF-23) activity have been proposed as contributors to HF [54]. Among patients with established HF, osteoporosis—particularly osteoporotic BMD at multiple skeletal sites—has been associated with a higher risk of death or HF hospitalization [42].
6. Therapeutic Interactions and Clinical Implications
Medication use is another consideration in cardiovascular–bone interactions. Treatments prescribed for CVDs or osteoporosis may affect processes relevant to both vascular and skeletal health. Some CVD medications influence bone metabolism through altering calcium processing, oxidative stress and inhibiting pathways, whereas osteoporosis medication can also affect cardiovascular physiology by affecting calcium balance, endothelial function, and inflammatory pathways [44].
6.1. Effects of Cardiovascular Therapies on Bone Health
Statins lower lipids by inhibiting HMG-CoA reductase and the production of mevalonate during cholesterol synthesis [76]. Statins primarily reduce LDL-C, with more modest effects on triglycerides and HDL-C, reducing the incidence of cardiovascular events. Statin use has also been associated with higher BMD and a lower risk of fracture in some studies. Increased BMP-2 expression and osteoblast differentiation have been proposed as pathways through which statins might promote bone formation [2] and exert bone-protective effects [76]. In an observational comparison, higher-potency statin use was associated with a lower risk of osteoporosis than lower-potency statin use [77].
Loop diuretics increase urinary calcium loss, which may lower serum calcium and raise parathyroid hormone (PTH) levels [76]. In a study of older patients evaluated for HF, loop diuretic use was associated with greater odds of osteoporosis after adjustment for medication use, sex, age, and weight (OR 2.52, 95% CI 1.20–5.27) [42].
Beta-blockers reduce sympathetic nervous system (SNS) activity in the treatment of HF. SNS stimulation increases osteoclast activity through increased RANKL expression, whereas beta-blockade may reduce this effect and thereby benefit bone health [78]. In the Framingham study, beta-blockers were found to increase bone density at the spine and femur depending on dosage. Beta-blocker therapy in postmenopausal women was found to decrease the bone resorption marker (C-telopeptide) and improve bone microarchitecture [76,78]. The Framingham findings support an association between beta-blocker use and higher BMD, but do not themselves establish a reduction in fracture risk. Reduced adrenergic signaling in osteoblasts, potentially accompanied by lower RANKL production, has been proposed as one explanation for the observed bone effects [76].
Vitamin K antagonists (VKAs), including warfarin, have been associated with a higher risk of osteoporotic fracture in some older populations [79]. Warfarin inhibits vitamin K recycling, reducing the carboxylation of vitamin K–dependent proteins involved in bone and vascular mineralization. Reduced activation of matrix Gla protein (MGP) may alter the regulation of arterial calcification; coronary artery and cardiac valve calcification have also been reported in relation to warfarin use [49]. Inhibition of vitamin K-dependent carboxylation of proteins associated with bone metabolism compromises bone quality [79].
6.2. Cardiovascular Effects of Osteoporosis Therapies
Treatments for osteoporosis have been found to have an effect on cardiovascular health (Table 2). Bisphosphonates used as first-line therapeutic agents for treating osteoporosis have been found to increase AF risk [9]. In a nationwide Taiwanese cohort of patients with osteoporosis and prior acute coronary syndrome or acute ischemic stroke, bisphosphonate use was associated with lower all-cause mortality, although hospitalization for AF was more frequent among users [80].
Glucocorticoids are a risk factor for osteoporosis and atherosclerosis. Dexamethasone downregulates calcification inhibitors like OPN and MGP, therefore inducing calcification. Estrogens are involved in the vascular calcification process, and studies have shown that the BMP osteogenic pathway is blocked by the increase in MGP mRNA expression due to estrogen replacement therapy. Estrogens have a direct effect on vascular endothelial and bone cells, as estrogen receptors are expressed on osteoblasts, osteoclasts, SMCs and vascular endothelial cells [49]. Studies have shown how estrogen replacement in postmenopausal women decreases the risk of fractures by increasing bone mineral density. Estrogen deficiency is associated with increased bone resorption as well as vascular dysfunction, which leads to hypertension [44].
New treatment approaches with distinct mechanisms have been identified through the discovery of key pathways which regulate bone resorption and formation [4]. Manipulating the OPG/RANKL pathway is a treatment approach for bone health and vascular calcification [12]. Trial results suggested that clinical management of postmenopausal women with osteoporosis should not focus on fracture prevention but also cardiovascular disease prevention [19].
7. Knowledge Gaps and Future Directions
7.1. Subtype-Specific Longitudinal Evidence
CVD and osteoporosis share several biological pathways, but their observed association may also reflect aging, physical inactivity, medication use, hormonal changes, renal dysfunction, and socioeconomic conditions. Because many studies treat CVD as a single category, it remains difficult to determine whether its subtypes differ in their associations with bone loss and fracture. Longitudinal studies could examine changes in BMD and fracture risk separately after CAD/MI, AF, HF, stroke, and PAD. The pathways may differ: inflammation, limited mobility, and loop diuretic use may be relevant in HF, whereas weakness, impaired balance, and falls may be particularly important after stroke. Comparing these trajectories could help identify patients who may benefit from closer assessment of skeletal health.
7.2. Mechanistic Gaps
Further work is needed to determine which mechanisms account for cardiovascular–bone interactions in different CVD subtypes. Inflammation, oxidative stress, vascular calcification, endocrine changes, and endothelial dysfunction are possible contributors, but their relative roles remain unclear. The RANK/RANKL/OPG and Wnt/β-catenin pathways merit particular attention because they are involved in bone remodeling and have also been implicated in vascular smooth muscle cell changes and calcification. Studies that measure biomarkers and imaging findings alongside clinical outcomes could help distinguish pathways shared across subtypes from those specific to a particular condition.
7.3. Genetic Evidence and Causal Inference
GWAS may identify genetic loci associated with individual CVD subtypes, osteoporosis, or BMD. Colocalization analyses can then assess whether associations for cardiovascular and skeletal traits at a given genomic region are consistent with a shared genetic signal. Mendelian randomization may provide additional evidence about whether genetically proxied cardiovascular traits influence skeletal outcomes, or the reverse, provided its assumptions are examined carefully.
7.4. Therapeutic Evidence
Managing CVD and osteoporosis together can be challenging in older adults. Treatment decisions must account for both conditions, particularly when a drug used for one may affect the other. Anticoagulants, loop diuretics, and statins have each been studied for possible effects on bone metabolism or fracture risk, while osteoporosis treatments, including bisphosphonates and hormone therapy, may have cardiovascular effects. Findings vary across treatments and study populations, and may depend on treatment duration, baseline disease severity, and adherence. When randomized trials are unavailable or infeasible, target trial emulation using well-characterized observational data could help compare treatment strategies, although residual confounding would remain a concern. More evidence is needed to inform treatment choices for patients who have both cardiovascular and skeletal disease.
7.5. Large-Scale Multimodal Data and Translation
Large-scale databases like the UK Biobank and All of Us Research Program can be used to answer the questions regarding the association between cardiovascular disease subtypes and osteoporosis. These databases can be used to assess the relationship across different populations enabling cross-cohort comparisons which can highlight differences influenced by variations in ancestry, sex, healthcare services, etc. Stratified analysis can also highlight differences in the cardiovascular-bone interactions across groups based on age, sex, comorbidities, race and menopausal status among others. Artificial intelligence and machine learning techniques could be used to investigate the relationship between CVD subtypes and osteoporosis through the integration of clinical, laboratory, genomic, and imaging data. Multimodal prediction models can be used to further study this relationship to help identify individuals with different CVD subtypes.
Future research encompassing a combination of causal inference methods, longitudinal cohorts, imaging, genetic analysis, and biomarkers’ predictive models will help improve the understanding of the cardiovascular-bone interactions, in this case cardiovascular disease subtypes and osteoporosis. This will help highlight intricate details regarding mechanisms, direction, and clinical implications of the relationship. The findings can help in the development of integrated screening and treatment of osteoporosis among patients based on the cardiovascular disease subtype they have while patients with osteoporosis also receive cardiovascular disease evaluation. These findings could inform earlier detection, prevention, more targeted treatment, and better coordination of cardiovascular and skeletal care.
8. Conclusion
Available evidence points to an association between CVD and osteoporosis, although its strength and direction may differ across cardiovascular subtypes. Inflammation, oxidative stress, and vascular calcification are among the proposed mechanisms linking vascular and skeletal health. Large cohorts, genomic studies, and causal inference methods are helping to examine these relationships in greater detail. Further subtype-specific research is needed to clarify the underlying pathways and determine whether the findings can improve prevention, early detection, and management of CVD and osteoporosis.
Sources of Funding: This research was in part supported by grants from the National Institutes of Health, USA (1R15HL172198, 1R15HL173852, and U19AG055373) and Blue Cross Blue Shield of Michigan Foundation (2025110031.SAP).
References
- Chong, B.; Jayabaskaran, J.; Jauhari, S.M.; Chan, S.P.; Goh, R.; Kueh, M.T.W.; Li, H.; Chin, Y.H.; Kong, G.; Anand, V.V.; Wang, J.-W.; Muthiah, M.; Jain, V.; Mehta, A.; Lim, S.L.; Foo, R.; Figtree, G.A.; Nicholls, S.J.; Mamas, M.A.; Januzzi, J.L.; Chew, N.W.S.; Richards, A.M.; Chan, M.Y. Global burden of cardiovascular diseases: projections from 2025 to 2050. Eur. J. Prev. Cardiol. 2025, 32(11), 1001–15. [Google Scholar] [CrossRef] [PubMed]
- Farhat, G.N.; Cauley, J.A. The link between osteoporosis and cardiovascular disease. Clin. Cases Min. Bone Metab.;PubMed 2008, 5(1), 19–34. [Google Scholar] [PubMed]
- Karunathilake, S.P.; Ganegoda, G.U. Secondary Prevention of Cardiovascular Diseases and Application of Technology for Early Diagnosis. BioMed Res. Int. 2018, 2018, 1–9. [Google Scholar] [CrossRef] [PubMed]
- Compston, J.E.; McClung, M.R.; Leslie, W.D. Osteoporosis. The Lancet 2019, 393(10169), 364–76. [Google Scholar] [CrossRef] [PubMed]
- Gregson, C.L.; Armstrong, D.J.; Bowden, J.; Cooper, C.; Edwards, J.; Gittoes, N.J.L.; Harvey, N.; Kanis, J.; Leyland, S.; Low, R.; McCloskey, E.; Moss, K.; Parker, J.; Paskins, Z.; Poole, K.; Reid, D.M.; Stone, M.; Thomson, J.; Vine, N.; Compston, J. UK clinical guideline for the prevention and treatment of osteoporosis. Arch. Osteoporos. 2022, 17(1). [Google Scholar] [CrossRef] [PubMed]
- LeBoff, M.S.; Greenspan, S.L.; Insogna, K.L.; Lewiecki, E.M.; Saag, K.G.; Singer, A.J.; Siris, E.S. The clinician’s guide to prevention and treatment of osteoporosis. Osteoporos. Int. 2022, 33(10), 2049–102. [Google Scholar] [CrossRef] [PubMed]
- Yang, Y.; Huang, Y. Association between bone mineral density and cardiovascular disease in older adults. Front. Public Health 2023, 11. [Google Scholar] [CrossRef] [PubMed]
- Zhang, J.; Xu, P.; Liu, R.; Gyu, J.M.; Cao, P.; Kang, C. Osteoporosis and coronary heart disease: a bi-directional Mendelian randomization study. Front. Endocrinol. 2024, 15. [Google Scholar] [CrossRef] [PubMed]
- Bhatta, L.; Cepelis, A.; Vikjord, S.A.; Malmo, V.; Laugsand, L.E.; Dalen, H.; Langhammer, A.; Janszky, I.; Strand, L.B.; Brumpton, B.M. Bone mineral density and risk of cardiovascular disease in men and women: the HUNT study. Eur. J. Epidemiol. 2021, 36(11), 1169–77. [Google Scholar] [CrossRef] [PubMed]
- Xing, W.; Lv, X.; Gao, W.; Wang, J.; Yang, Z.; Wang, S.; Zhang, J.; Yan, J. Bone mineral density in patients with chronic heart failure: a meta-analysis. Clin. Interv. Aging 2018, Volume 13, 343–53. [Google Scholar] [CrossRef] [PubMed]
- Veronese, N.; Stubbs, B.; Crepaldi, G.; Solmi, M.; Cooper, C.; Harvey, N.C.W.; Reginster, J.-Y.; Rizzoli, R.; Civitelli, R.; Schofield, P.; Maggi, S.; Lamb, S.E. Relationship Between Low Bone Mineral Density and Fractures With Incident Cardiovascular Disease: A Systematic Review and Meta-Analysis. J. Bone Mineral. Res. 2017, 32(5), 1126–35. [Google Scholar] [CrossRef] [PubMed]
- West, S.L.; O’Donnell, E. Cardiovascular disease and bone loss—new research in identifying common disease pathophysiologies and predictors. AME Med. J. 2018, 3, 42. [Google Scholar] [CrossRef]
- Wong, C.X.; Gan, S.W.; Lee, S.W.; Gallagher, C.; Kinnear, N.J.; Lau, D.H.; Mahajan, R.; Roberts-Thomson, K.C.; Sanders, P. Atrial fibrillation and risk of hip fracture: A population-based analysis of 113,600 individuals. Int. J. Cardiol. 2017, 243, 229–32. [Google Scholar] [CrossRef] [PubMed]
- Sennerby, U.; Farahmand, B.; Ahlbom, A.; Ljunghall, S.; Michaëlsson, K. Cardiovascular diseases and future risk of hip fracture in women. Osteoporos. Int. 2007, 18(10), 1355–62. [Google Scholar] [CrossRef] [PubMed]
- Sennerby, U. Cardiovascular Diseases and Risk of Hip Fracture. JAMA 2009, 302(15), 1666. [Google Scholar] [CrossRef] [PubMed]
- Laroche, M.; Pécourneau, V.; Blain, H.; Breuil, V.; Chapurlat, R.; Cortet, B.; Sutter, B.; Degboe, Y. Osteoporosis and ischemic cardiovascular disease. Jt. Bone Spine 2017, 84(4), 427–32. [Google Scholar] [CrossRef] [PubMed]
- Sprini, D. Correlation between osteoporosis and cardiovascular disease. Clin. Cases Mineral. Bone Metab. 2014. [Google Scholar] [CrossRef]
- Gupta, G.; Aronow, W.S. Atherosclerotic vascular disease may be associated with osteoporosis or osteopenia in postmenopausal women: A preliminary study. Arch. Gerontol. Geriatr. 2006, 43(2), 285–8. [Google Scholar] [CrossRef] [PubMed]
- Tankó, L.B.; Christiansen, C.; Cox, D.A.; Geiger, M.J.; McNabb, M.A.; Cummings, S.R. Relationship Between Osteoporosis and Cardiovascular Disease in Postmenopausal Women. J. Bone Mineral. Res. 2005, 20(11), 1912–20. [Google Scholar] [CrossRef] [PubMed]
- Park, J.; Yoon, Y.E.; Kim, K.M.; Hwang, I.-C.; Lee, W.; Cho, G.-Y. Prognostic value of lower bone mineral density in predicting adverse cardiovascular disease in Asian women. Heart 2021, 107(13), 1040–6. [Google Scholar] [CrossRef] [PubMed]
- Xu, B.; Han, L.; Liu, H.; Wang, J.; Bao, X.-Y.; Xi, H.-X.; Zhao, L.; Yu, G.-P. Cardiovascular Disease and Hip Fracture among Older Inpatients in Beijing, China. BioMed Res. Int. 2013, 2013, 1–6. [Google Scholar] [CrossRef] [PubMed]
- Frąk, W.; Wojtasińska, A.; Lisińska, W.; Młynarska, E.; Franczyk, B.; Rysz, J. Pathophysiology of Cardiovascular Diseases: New Insights into Molecular Mechanisms of Atherosclerosis, Arterial Hypertension, and Coronary Artery Disease. Biomedicines 2022, 10(8), 1938. [Google Scholar] [CrossRef] [PubMed]
- Azeez, T.A. Osteoporosis and cardiovascular disease: a review. Mol. Biol. Rep. 2023, 50(2), 1753–63. [Google Scholar] [CrossRef] [PubMed]
- Marcovitz, P.A.; Tran, H.H.; Franklin, B.A.; O’Neill, W.W.; Yerkey, M.; Boura, J.; Kleerekoper, M.; Dickinson, C.Z. Usefulness of Bone Mineral Density to Predict Significant Coronary Artery Disease. Am. J. Cardiol. 2005, 96(8), 1059–63. [Google Scholar] [CrossRef] [PubMed]
- Fiechter, M.; Bengs, S.; Roggo, A.; Haider, A.; Marędziak, M.; Portmann, A.; Treyer, V.; Burger, I.A.; Messerli, M.; Patriki, D.; von Felten, E.; Benz, D.C.; Fuchs, T.A.; Gräni, C.; Pazhenkottil, A.P.; Buechel, R.R.; Kaufmann, P.A.; Gebhard, C. Association between vertebral bone mineral density, myocardial perfusion, and long-term cardiovascular outcomes: A sex-specific analysis. J. Nucl. Cardiol. 2020, 27(3), 726–36. [Google Scholar] [CrossRef] [PubMed]
- Sacco, R.L.; Kasner, S.E.; Broderick, J.P.; Caplan, L.R.; Connors, J.J.; Culebras, A.; Elkind, M.S.V.; George, M.G.; Hamdan, A.D.; Higashida, R.T.; Hoh, B.L.; Janis, L.S.; Kase, C.S.; Kleindorfer, D.O.; Lee, J.-M.; Moseley, M.E.; Peterson, E.D.; Turan, T.N.; Valderrama, A.L.; Vinters, H.V. An Updated Definition of Stroke for the 21st Century. Stroke 2013, 44(7), 2064–89. [Google Scholar] [CrossRef] [PubMed]
- Coupland, A.P.; Thapar, A.; Qureshi, M.I.; Jenkins, H.; Davies, A.H. The definition of stroke. J. R. Soc. Med. 2017, 110(1), 9–12. [Google Scholar] [CrossRef] [PubMed]
- Murphy, S.J.X.; Werring, D.J. Stroke: causes and clinical features. Medicine 2020, 48(9), 561–6. [Google Scholar] [CrossRef] [PubMed]
- Jørgensen, L.; Engstad, T.; Jacobsen, B.K. Bone Mineral Density in Acute Stroke Patients. Stroke 2001, 32(1), 47–51. [Google Scholar] [CrossRef] [PubMed]
- Wang, J.; Sun, Y.; Guo, X.; Zhang, Z.; Liang, H.; Zhang, T. The effect of stroke on the bone mineral density: A systematic review and meta-analysis. J. Nutr. Health Aging;PubMed 2024, 28(4), 100189. [Google Scholar] [CrossRef] [PubMed]
- Liu, B.; Ng, C.Y.; La, P.B.D.; Wong, P.; Ebeling, P.R.; Singhal, S.; Phan, T.; Trinh, A.; Milat, F. Osteoporosis and fracture risk assessment in adults with ischaemic stroke. Osteoporos. Int. 2024, 35(7), 1243–7. [Google Scholar] [CrossRef] [PubMed]
- Lee, D.; Cho, I.Y.; Chang, W.H.; Yoo, J.E.; Choi, H.L.; Park, J.; Shin, D.W.; Han, K. Fracture Risk Among Stroke Survivors According to Poststroke Disability Status and Stroke Type. Stroke 2024, 55(6), 1498–506. [Google Scholar] [CrossRef] [PubMed]
- Yu, Q.; Yi, Y.; Li, Y.; Wang, J.; Liu, S.; Lu, J.; Ouyang, C.; Zhong, X.; Yuan, H.; Lu, Y. Bone mineral loss and risk of atrial fibrillation: a multicohort study. Eur. J. Prev. Cardiol. 2025. [Google Scholar] [CrossRef] [PubMed]
- Joglar, J.A.; Chung, M.K.; Armbruster, A.L.; Benjamin, E.J.; Chyou, J.Y.; Cronin, E.M.; Deswal, A.; Eckhardt, L.L.; Goldberger, Z.D.; Gopinathannair, R.; Gorenek, B.; Hess, P.L.; Hlatky, M.; Hogan, G.; Ibeh, C.; Indik, J.H.; Kido, K.; Kusumoto, F.; Link, M.S.; Linta, K.T.; Marcus, G.M.; McCarthy, P.M.; Patel, N.; Patton, K.K.; Perez, M.V.; Piccini, J.P.; Russo, A.M.; Sanders, P.; Streur, M.M.; Thomas, K.L.; Times, S.; Tisdale, J.E.; Valente, A.M.; Van Wagoner, D.R. 2023 ACC/AHA/ACCP/HRS Guideline for the Diagnosis and Management of Atrial Fibrillation: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation 2024, 149(1). [Google Scholar] [CrossRef] [PubMed]
- Kim, D.; Yang, P.-S.; Kim, T.-H.; Uhm, J.-S.; Park, J.; Pak, H.-N.; Lee, M.-H.; Joung, B. Effect of Atrial Fibrillation on the Incidence and Outcome of Osteoporotic Fracture ― A Nationwide Population-Based Study ―. Circ. J. 2018, 82(8), 1999–2006. [Google Scholar] [CrossRef] [PubMed]
- Wallace, E.R.; Siscovick, D.S.; Sitlani, C.M.; Dublin, S.; Mitchell, P.; Robbins, J.A.; Fink, H.A.; Cauley, J.A.; Bůžková, P.; Carbone, L.; Chen, Z.; Heckbert, S.R. Incident atrial fibrillation and the risk of fracture in the cardiovascular health study. Osteoporos. Int.;PubMed 2017, 28(2), 719–25. [Google Scholar] [CrossRef] [PubMed]
- Shu, J.; Santulli, G. Update on peripheral artery disease: Epidemiology and evidence-based facts. Atherosclerosis 2018, 275, 379–81. [Google Scholar] [CrossRef] [PubMed]
- Ungprasert, P.; Wijarnpreecha, K.; Thongprayoon, C.; Cheungpasitporn, W. Peripheral arterial disease and risk of hip fracture. J. Postgrad. Med. 2018, 64(4), 220–5. [Google Scholar] [CrossRef] [PubMed]
- von Mühlen, D.; Allison, M.; Jassal, S.K.; Barrett-Connor, E. Peripheral arterial disease and osteoporosis in older adults: the Rancho Bernardo Study. Osteoporos. Int. 2009, 20(12), 2071–8. [Google Scholar] [CrossRef] [PubMed]
- Syu, D.-K.; Hsu, S.-H.; Yeh, P.-C.; Lee, T.-L.; Kuo, Y.-F.; Huang, Y.-C.; Jiang, C.-C.; Chen, M. The Association between Osteoporosis and Peripheral Artery Disease: A Population-Based Longitudinal Follow-Up Study in Taiwan. Int. J. Environ. Res. Public Health 2022, 19(18), 11327. [Google Scholar] [CrossRef] [PubMed]
- Heidenreich, P.A.; Bozkurt, B.; Aguilar, D.; Allen, L.A.; Byun, J.J.; Colvin, M.M.; Deswal, A.; Drazner, M.H.; Dunlay, S.M.; Evers, L.R.; Fang, J.C.; Fedson, S.E.; Fonarow, G.C.; Hayek, S.S.; Hernandez, A.F.; Khazanie, P.; Kittleson, M.M.; Lee, C.S.; Link, M.S.; Milano, C.A.; Nnacheta, L.C.; Sandhu, A.T.; Stevenson, L.W.; Vardeny, O.; Vest, A.R.; Yancy, C.W. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation;PubMed 2022, 145(18), e895–e1032. [Google Scholar] [CrossRef] [PubMed]
- Katano, S.; Yano, T.; Tsukada, T.; Kouzu, H.; Honma, S.; Inoue, T.; Takamura, Y.; Nagaoka, R.; Ishigo, T.; Watanabe, A.; Ohori, K.; Koyama, M.; Nagano, N.; Fujito, T.; Nishikawa, R.; Takashima, H.; Hashimoto, A.; Katayose, M.; Miura, T. Clinical Risk Factors and Prognostic Impact of Osteoporosis in Patients With Chronic Heart Failure. Circ. Journal. 2020, 84(12), 2224–34. [Google Scholar] [CrossRef] [PubMed]
- Cauley, J.A.; Danielson, M.E.; Boudreau, R.M.; Forrest, K.Y.Z.; Zmuda, J.M.; Pahor, M.; Tylavsky, F.A.; Cummings, S.R.; Harris, T.B.; Newman, A.B. Inflammatory Markers and Incident Fracture Risk in Older Men and Women: The Health Aging and Body Composition Study. J. Bone Mineral. Res. 2007, 22(7), 1088–95. [Google Scholar] [CrossRef] [PubMed]
- Gutierrez, Y.; Shaju, R.A.; Sepulveda, A.; Coban, S. Exploring the Interplay Between Hypertension and Osteoporosis: A Narrative Review. Cureus 2025. [Google Scholar] [CrossRef] [PubMed]
- Luo, J.; Li, L.; Shi, W.; Xu, K.; Shen, Y.; Dai, B. Oxidative stress and inflammation: roles in osteoporosis. Front. Immunol. 2025, 16. [Google Scholar] [CrossRef] [PubMed]
- Mkhize, B.C.; Mosili, P.; Ngubane, P.S.; Sibiya, N.H.; Khathi, A. The Relationship between Renin–Angiotensin–Aldosterone System (RAAS) Activity, Osteoporosis and Estrogen Deficiency in Type 2 Diabetes. Int. J. Mol. Sci. 2023, 24(15), 11963. [Google Scholar] [CrossRef] [PubMed]
- Rodrigo, R.; González, J.; Paoletto, F. The role of oxidative stress in the pathophysiology of hypertension. Hypertens. Res. 2011, 34(4), 431–40. [Google Scholar] [CrossRef] [PubMed]
- Qi, J.; Li, R.-J.; Fu, L.-Y.; Liu, K.-L.; Qiao, J.-A.; Yang, Y.; Yu, X.-J.; Yu, J.-Y.; Li, Y.; Tan, H.; Kang, Y.-M. Exercise Training Attenuates Hypertension via Suppressing ROS/MAPK/NF-κB/AT-1R Pathway in the Hypothalamic Paraventricular Nucleus. Nutrients 2022, 14(19), 3968. [Google Scholar] [CrossRef] [PubMed]
- Lampropoulos, C.E.; Papaioannou, I.; D’Cruz, D.P. Osteoporosis—a risk factor for cardiovascular disease? Nat. Rev. Rheumatol. 2012, 8(10), 587–98. [Google Scholar] [CrossRef] [PubMed]
- Stojanovic, O.I.; Lazovic, M.; Lazovic, M.; Vuceljic, M. Association between atherosclerosis and osteoporosis, the role of vitamin D. Arch. Med. Sci. 2011, 2, 179–88. [Google Scholar] [CrossRef] [PubMed]
- Osako, M.K.; Nakagami, H.; Koibuchi, N.; Shimizu, H.; Nakagami, F.; Koriyama, H.; Shimamura, M.; Miyake, T.; Rakugi, H.; Morishita, R. Estrogen Inhibits Vascular Calcification via Vascular RANKL System. Circ. Res. 2010, 107(4), 466–75. [Google Scholar] [CrossRef] [PubMed]
- Theoleyre, S.; Wittrant, Y.; Tat, S.K.; Fortun, Y.; Redini, F.; Heymann, D. The molecular triad OPG/RANK/RANKL: involvement in the orchestration of pathophysiological bone remodeling. Cytokine Amp Growth Factor Rev. 2004, 15(6), 457–75. [Google Scholar] [CrossRef] [PubMed]
- Carbone, L.D.; Vasan, S.; Prentice, R.L.; Harshfield, G.; Haring, B.; Cauley, J.A.; Johnson, K.C. The renin-angiotensin aldosterone system and osteoporosis: findings from the Women’s Health Initiative. Osteoporos. Int. 2019, 30(10), 2039–56. [Google Scholar] [CrossRef] [PubMed]
- Spoladore, R.; Ciampi, C.M.; Ossola, P.; Sultana, A.; Spreafico, L.P.; Farina, A.; Fragasso, G. Heart Failure and Osteoporosis: Shared Challenges in the Aging Population. J. Cardiovasc. Dev. Dis. 2025, 12(2), 69. [Google Scholar] [CrossRef] [PubMed]
- Nakashima, T.; Hayashi, M.; Takayanagi, H. New insights into osteoclastogenic signaling mechanisms. Trends Endocrinol. Amp Metab. 2012, 23(11), 582–90. [Google Scholar] [CrossRef] [PubMed]
- Hofbauer, L.C.; Khosla, S.; Dunstan, C.R.; Lacey, D.L.; Boyle, W.J.; Riggs, B.L. The Roles of Osteoprotegerin and Osteoprotegerin Ligand in the Paracrine Regulation of Bone Resorption. J. Bone Mineral. Res. 2000, 15(1), 2–12. [Google Scholar] [CrossRef] [PubMed]
- Bjerre, M.; Hilden, J.; Kastrup, J.; Skoog, M.; Hansen, J.F.; Kolmos, H.J.; Jensen, G.B.; Kjøller, E.; Winkel, P.; Flyvbjerg, A.; Gluud, C.; The Claricor Trial G. Osteoprotegerin independently predicts mortality in patients with stable coronary artery disease: The CLARICOR trial. Scand. J. Clin. Lab. Investig. 2014, 74(8), 657–64. [Google Scholar] [CrossRef] [PubMed]
- Cao, L.; Wang, J. Roles of Wnt/β-Catenin Signaling in Osteoporosis, Disease Pathogenesis, and Natural Compound Intervention. Biomol. Amp Ther. 2026, 34(1), 65–79. [Google Scholar] [CrossRef] [PubMed]
- Manolagas, S.C. Wnt signaling and osteoporosis. Maturitas 2014, 78(3), 233–7. [Google Scholar] [CrossRef] [PubMed]
- Gay, A.; Towler, D.A. Wnt signaling in cardiovascular disease: opportunities and challenges. Curr. Opin. Lipidol. 2017, 28(5), 387–96. [Google Scholar] [CrossRef] [PubMed]
- Liu, Y.; Neogi, A.; Mani, A. The role of Wnt signalling in development of coronary artery disease and its risk factors. Open Biol. 2020, 10(10). [Google Scholar] [CrossRef] [PubMed]
- Valdes, A.M.; Richards, J.B.; Gardner, J.P.; Swaminathan, R.; Kimura, M.; Xiaobin, L.; Aviv, A.; Spector, T.D. Telomere length in leukocytes correlates with bone mineral density and is shorter in women with osteoporosis. Osteoporos. Int. 2007, 18(9), 1203–10. [Google Scholar] [CrossRef] [PubMed]
- Haycock, P.C.; Heydon, E.E.; Kaptoge, S.; Butterworth, A.S.; Thompson, A.; Willeit, P. Leucocyte telomere length and risk of cardiovascular disease: systematic review and meta-analysis. BMJ 2014, 349, g4227–g. [Google Scholar] [CrossRef] [PubMed]
- Kaur, J.; Rai, V.; Bhullar, G. The intersection of osteoporosis and cardiovascular disease in pathogenesis and treatment. Discov. Med. 2026, 3(1). [Google Scholar] [CrossRef]
- Estrada, K.; Styrkarsdottir, U.; Evangelou, E.; Hsu, Y.-H.; Duncan, E.L.; Ntzani, E.E.; Oei, L.; Albagha, O.M.E.; Amin, N.; Kemp, J.P.; et al. Genome-wide meta-analysis identifies 56 bone mineral density loci and reveals 14 loci associated with risk of fracture. Nature Genetics 2012, 44, 491–501. [Google Scholar] [CrossRef]
- Wang, X.; Qu, Z.; Zhao, S.; luo, L.; Yan, L. Wnt/β-catenin signaling pathway: proteins’ roles in osteoporosis and cancer diseases and the regulatory effects of natural compounds on osteoporosis. Mol. Med. 2024, 30(1). [Google Scholar] [CrossRef] [PubMed]
- Pang, M.Y.C.; Eng, J.J. Muscle strength is a determinant of bone mineral content in the hemiparetic upper extremity: implications for stroke rehabilitation. In Bone; PubMed PMID, 2005; Volume 37, 1, pp. 103–11. [Google Scholar] [CrossRef] [PubMed]
- Fan, Z.; Zhao, J.; Chen, J.; Hu, W.; Ma, J.; Ma, X. Causal associations of osteoporosis with stroke: a bidirectional Mendelian randomization study. Osteoporos. Int. 2024, 35(12), 2127–35. [Google Scholar] [CrossRef] [PubMed]
- Chung, M.E.; Lee, J.I.; Im, S.; Park, J.H. Ischemic stroke in rats enhances bone resorption in vitro. J. Korean Med. Sci.;PubMed 2012, 27(1), 84–8. [Google Scholar] [CrossRef] [PubMed]
- O’Neal, W.T.; Efird, J.T.; Dawood, F.Z.; Yeboah, J.; Alonso, A.; Heckbert, S.R.; Soliman, E.Z. Coronary artery calcium and risk of atrial fibrillation (from the Multi-Ethnic Study of Atherosclerosis). Am. J. Cardiol.;PubMed 2014, 114(11), 1707–12. [Google Scholar] [CrossRef] [PubMed]
- Lutsey, P.L.; Norby, F.L.; Ensrud, K.E.; MacLehose, R.F.; Diem, S.J.; Chen, L.Y.; Alonso, A. Association of Anticoagulant Therapy With Risk of Fracture Among Patients With Atrial Fibrillation. JAMA Intern. Med.;PubMed 2020, 180(2), 245–53. [Google Scholar] [CrossRef] [PubMed]
- Bokrantz, T.; Manhem, K.; Lorentzon, M.; Karlsson, M.; Ljunggren, Ö.; Ohlsson, C.; Mellström, D. The association between peripheral arterial disease and risk for hip fractures in elderly men is not explained by low hip bone mineral density. Results from the MrOS Sweden study. Osteoporos. Int.;PubMed 2022, 33(12), 2607–17. [Google Scholar] [CrossRef] [PubMed]
- Gardner, A.W.; Montgomery, P.S. Impaired balance and higher prevalence of falls in subjects with intermittent claudication. In The Journals of Gerontology: Series A; PubMed PMID, 2001; Volume 56, 7, pp. M454–M8. [Google Scholar] [CrossRef] [PubMed]
- Verheyen, N.; Schmid, J.; Kolesnik, E.; Schwegel, N.; Späth, J.; Kattnig, L.; Riepl, H.; Zach, D.; Santner, V.; Höller, V.; Pilz, S.; Tomaschitz, A.; Fuchsjäger, M.; Fahrleitner-Pammer, A.; Dimai, H.P.; Obermayer-Pietsch, B.; Fruhwald, F.; Scherr, D.; Zirlik, A.; von Lewinski, D.; Ablasser, K. Prevalence and Prognostic Impact of Bone Disease in Chronic Heart Failure with Reduced Ejection Fraction. ESC Heart Fail. 2024, 11(3), 1730–8. [Google Scholar] [CrossRef] [PubMed]
- Liu, X-p; Jian, X-y; Liang, D-l; Wen, J-x; Wei, Y-h; Wu, J-d; Li, Y.-Q. The association between heart failure and risk of fractures: Pool analysis comprising 260,410 participants. Front. Cardiovasc. Med. 2022, 9. [Google Scholar] [CrossRef] [PubMed]
- Trost, S.; Tesfaye, N.; Harindhanavudhi, T. The interplay between bone and heart health as reflected in medication effects: A narrative review. Women’s Health 2023, 19. [Google Scholar] [CrossRef] [PubMed]
- Jeong, J.S.; Noh, Y.; Cho, S.W.; Hsieh, C.-Y.; Cho, Y.; Shin, J.-Y.; Kim, H. Association of higher potency statin use with risk of osteoporosis and fractures in patients with stroke in a Korean nationwide cohort study. Sci. Rep. 2024, 14(1). [Google Scholar] [CrossRef] [PubMed]
- Khosla, S.; Drake, M.T.; Volkman, T.L.; Thicke, B.S.; Achenbach, S.J.; Atkinson, E.J.; Joyner, M.J.; Rosen, C.J.; Monroe, D.G.; Farr, J.N. Sympathetic β1-adrenergic signaling contributes to regulation of human bone metabolism. J. Clin. Investig. 2018, 128(11), 4832–42. [Google Scholar] [CrossRef] [PubMed]
- Tsai, S.H.L.; Hu, C.-W.; Shao, S.-C.; Tischler, E.H.; Obisesan, O.H.; Vervoort, D.; Chen, W.C.; Hu, J.-R.; Kuo, L.-T. Comparative Risks of Fracture Among Direct Oral Anticoagulants and Warfarin: A Systematic Review and Network Meta-Analysis. Front. Cardiovasc. Med. 2022, 9. [Google Scholar] [CrossRef] [PubMed]
- Wu, S.-T.; Chen, J.-F.; Tsai, C.-J. The impact of bisphosphonates on mortality and cardiovascular risk among osteoporosis patients after cardiovascular disease. J. Formos. Med. Assoc. 2021, 120(11), 1957–66. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Shared risk factors linking cardiovascular and bone health.
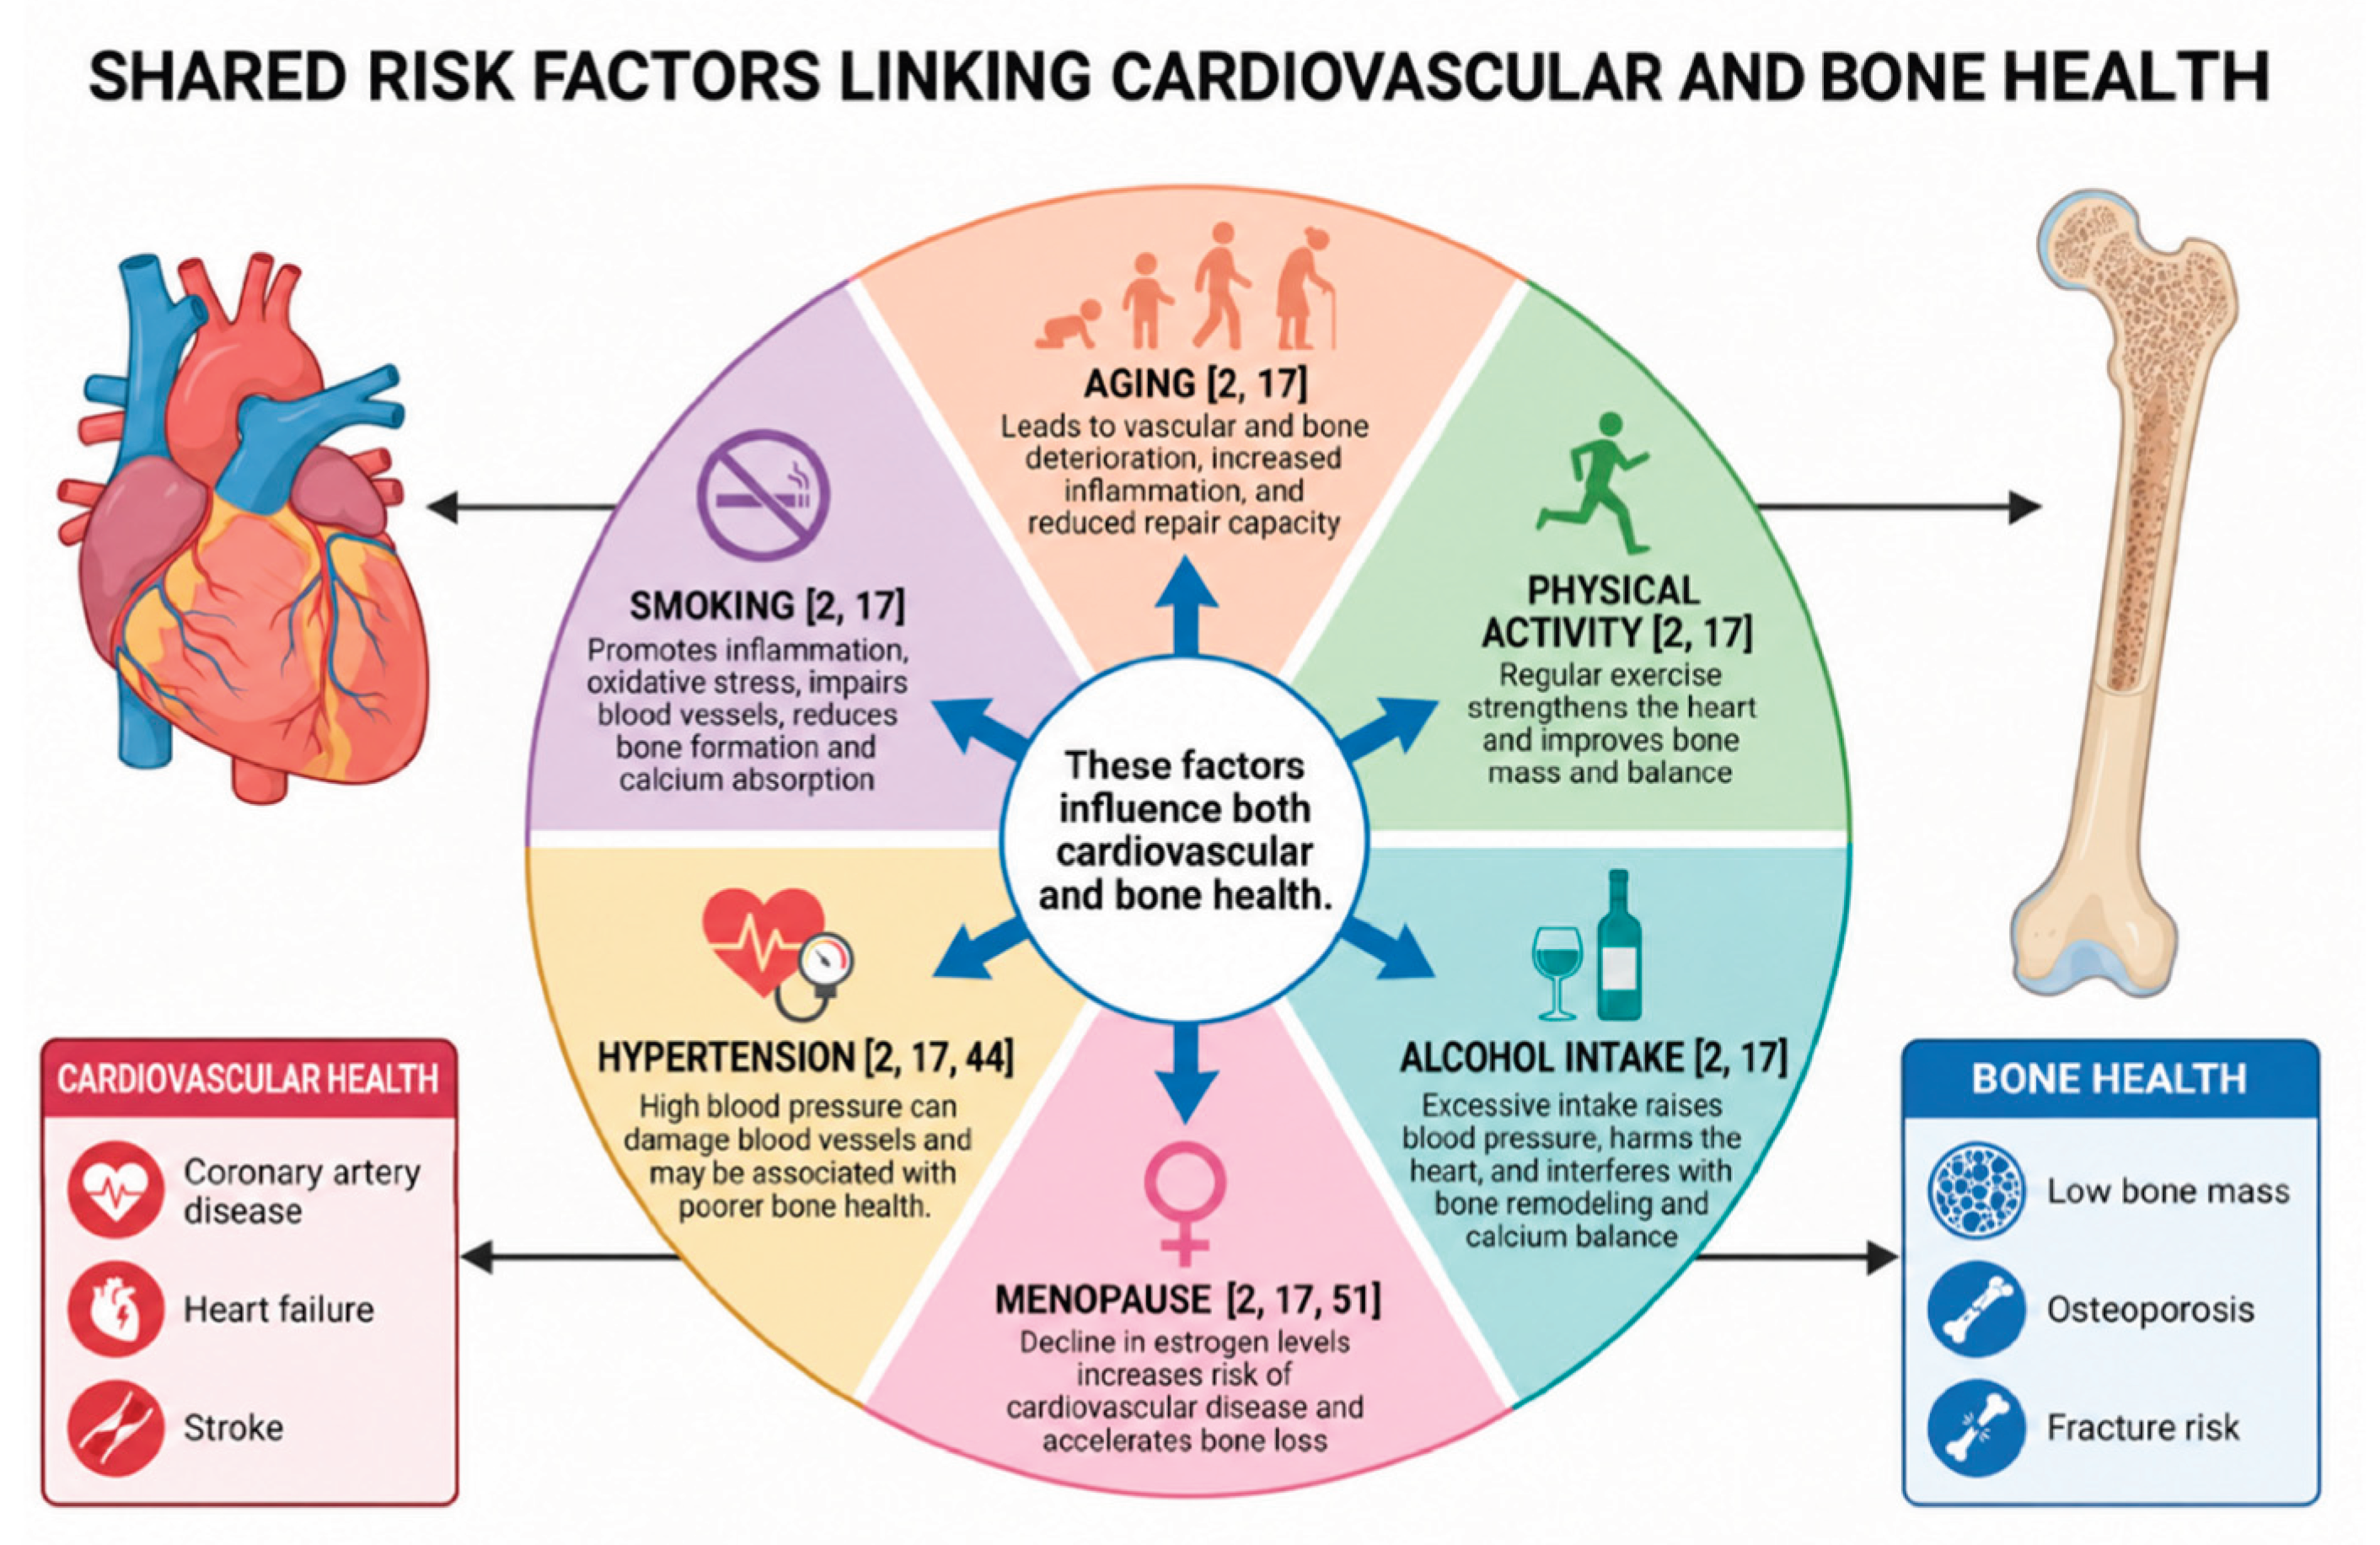
Figure 2.
Shared pathophysiological and biological mechanisms linking cardiovascular disease and osteoporosis. Chronic inflammation, oxidative stress, endocrine dysregulation, vascular calcification, and altered bone-remodeling pathways collectively contribute to cardiovascular dysfunction, bone loss, and an increased risk of osteoporosis and hip fracture.
Figure 2.
Shared pathophysiological and biological mechanisms linking cardiovascular disease and osteoporosis. Chronic inflammation, oxidative stress, endocrine dysregulation, vascular calcification, and altered bone-remodeling pathways collectively contribute to cardiovascular dysfunction, bone loss, and an increased risk of osteoporosis and hip fracture.
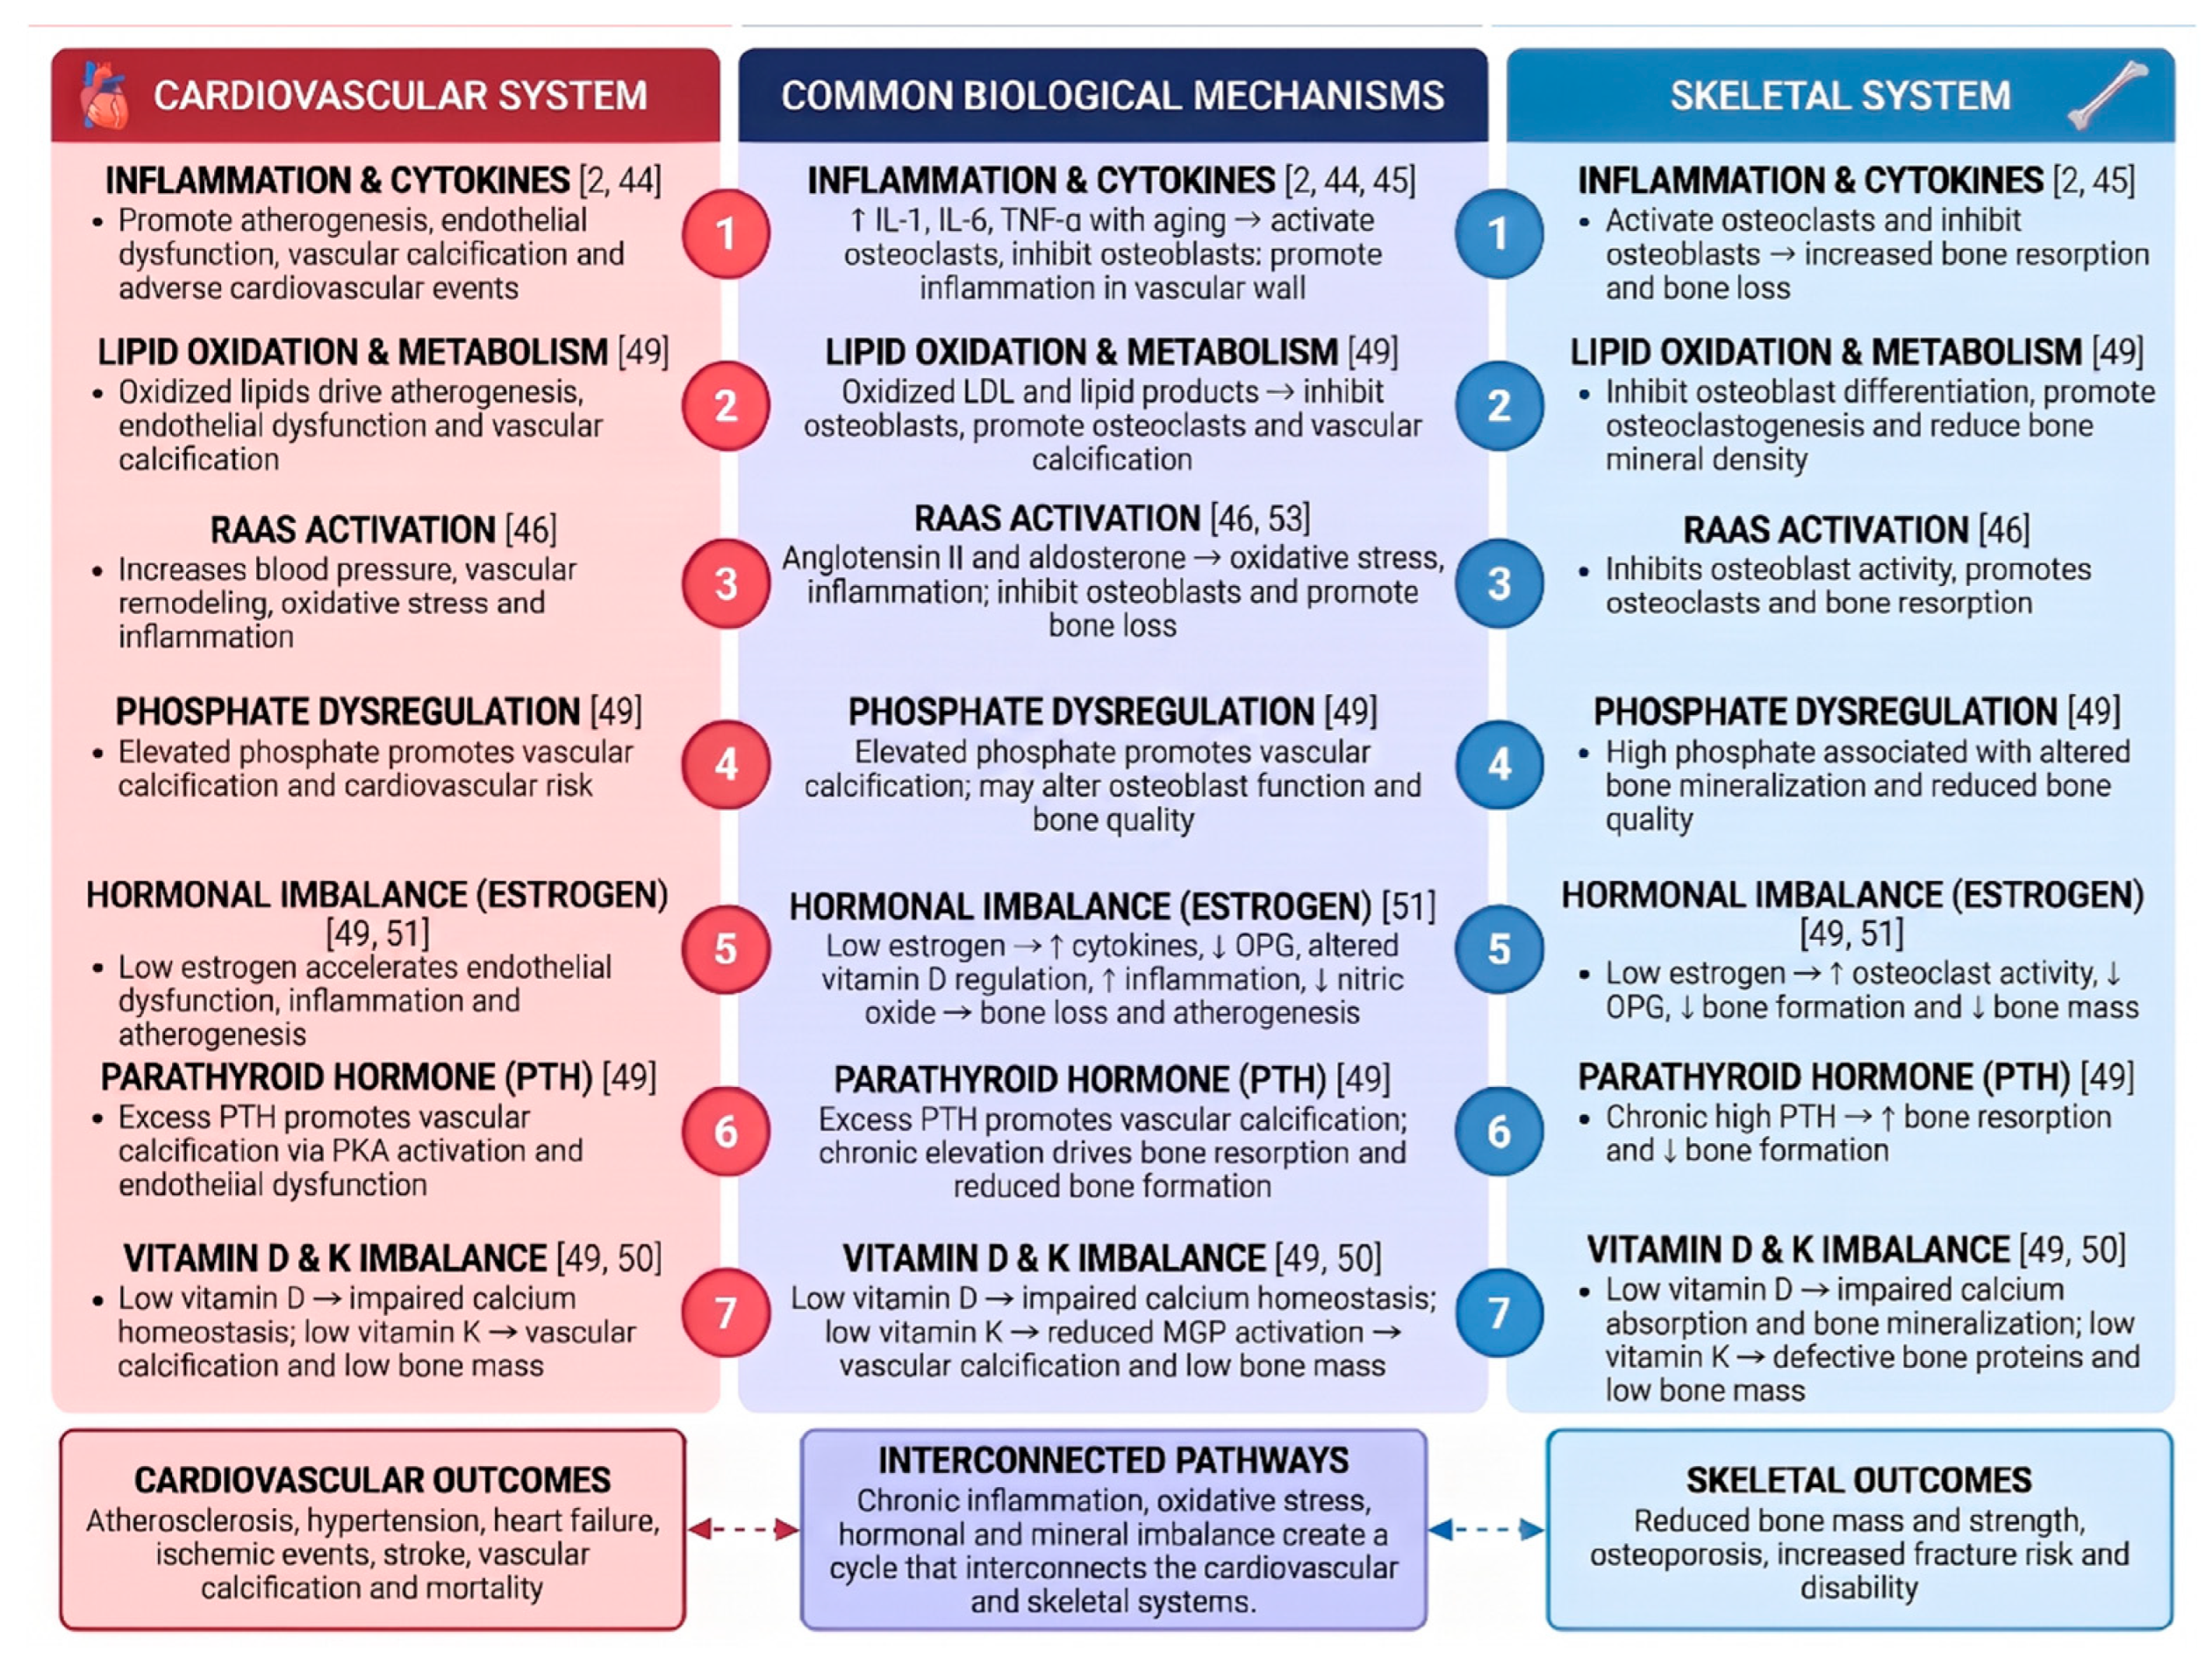

Table 1.
Shared pathophysiological factors between CVDs & Osteoporosis.
| Shared biological mechanism | Role in cardiovascular disease | Role in bone loss/osteoporosis |
| Inflammation and inflammatory cytokines | Chronic inflammation promotes endothelial dysfunction, atherosclerosis, and vascular remodeling. Elevated IL-1, IL-6, and TNF-α are associated with cardiovascular events and disease progression. | IL-1, IL-6, and TNF-α stimulate osteoclast differentiation and activity while suppressing osteoblast function, increasing bone resorption, and reducing bone formation. |
| Lipid oxidation and lipid metabolism | Oxidized LDL promotes endothelial dysfunction, atherosclerotic plaque formation, and vascular calcification. | Oxidized lipids inhibit osteoblast differentiation, enhance osteoclastogenesis, and are associated with reduced bone mineral density. |
| Vitamin D and Vitamin K | Vitamin D deficiency is associated with HF, while vitamin K deficiency contributes to vascular calcification through MGP activation interruption. | Vitamin D regulates calcium homeostasis and bone mineralization. Vitamin K is required for γ-carboxylation of bone proteins. |
| Phosphate homeostasis | Hyperphosphatemia promotes vascular calcification and increases cardiovascular morbidity and mortality. | Both phosphate deficiency and excess impair normal bone mineralization and alter bone quality. |
| Estrogen deficiency | Reduced estrogen increases inflammation, oxidative stress, and endothelial dysfunction, contributing to atherosclerosis. | Estrogen deficiency decreases OPG expression, increases osteoclast activity, and accelerates bone loss. |
| Parathyroid hormone (PTH) | Sustained elevation of PTH promotes vascular calcification. | Continuous PTH exposure stimulates bone resorption, whereas intermittent exposure promotes bone formation. |
| Renin–Angiotensin–Aldosterone System (RAAS) | RAAS activation contributes to hypertension, vascular remodeling, oxidative stress, and atherosclerosis. | Angiotensin II suppresses osteoblast maturation, increases RANKL expression and enhances osteoclast activity. |
| Vascular calcification and bone mineralization | Vascular smooth muscle cells undergo osteogenic differentiation, resulting in arterial calcification. | Increased bone resorption releases calcium and phosphate, contributing to deterioration of bone microarchitecture. |
| OPG/RANK/RANKL signaling pathway | Regulates vascular calcification, arterial stiffness, and cardiovascular mortality. | RANKL promotes osteoclastogenesis while OPG inhibits osteoclast differentiation. |
| Bone morphogenetic proteins (BMPs) | BMP-2 and BMP-4 promote osteogenic transformation of vascular smooth muscle cells. | BMPs regulate osteoblast differentiation, collagen synthesis, and bone formation. |
| Oxidative stress | Reactive oxygen species promote endothelial dysfunction, hypertension, and vascular remodeling. | Reactive oxygen species enhance osteoclastogenesis and suppress osteoblast differentiation. |
Table 2.
Effects of cardiovascular medication on osteoporosis.
| Medication class | Common examples | Primary mechanism of action | Impact on bone health | Mechanisms related to bone health |
| Thiazide and thiazide-like diuretics | Hydrochlorothiazide; chlorthalidone; indapamide | Inhibit the sodium–chloride cotransporter in the distal convoluted tubule, lowering blood pressure and reducing urinary calcium loss. | Increased bone mineral density and a lower risk of hip or other osteoporotic fractures. | Reduced urinary calcium excretion may improve calcium balance. Thiazides may promote osteoblast activity and bone formation. |
| Loop diuretics | Furosemide; bumetanide; torsemide | Block the sodium–potassium–chloride cotransporter in the thick ascending limb, producing strong natriuresis and diuresis. | Long-term exposure linked to increased bone loss and fracture risk | Increased urinary calcium excretion can stimulate secondary hyperparathyroidism and accelerate bone turnover. Dizziness and electrolyte disturbances may increase falls. |
| Beta-adrenergic blockers | Metoprolol; atenolol; carvedilol; propranolol | Block beta-adrenergic receptors, reducing heart rate, myocardial contractility and sympathetic activity. | Increases bone density, fewer fractures, | Reduced sympathetic signaling may decrease osteoclast activation and bone resorption. |
| Statins | Atorvastatin; rosuvastatin; simvastatin; pravastatin | Inhibit HMG-CoA reductase, reducing hepatic cholesterol synthesis and increasing LDL-receptor activity. | higher bone density and fewer fractures | Inhibition of the mevalonate pathway may reduce osteoclast prenylation and resorption. Statins promote bone morphogenetic protein-2 expression and osteoblast differentiation. |
| Angiotensin-converting enzyme inhibitors | Lisinopril; enalapril; ramipril | Reduce conversion of angiotensin I to angiotensin II and increase bradykinin, lowering vascular resistance and aldosterone activity. | Reduces osteoporosis, fracture risk and bone-density loss. | Lower angiotensin II activity reduces osteoclastogenesis, inflammation and oxidative stress |
| Angiotensin II receptor blockers | Losartan; valsartan; candesartan | Block angiotensin II type-1 receptors, reducing vasoconstriction, aldosterone release and vascular remodeling. | Reduces fracture risk | Reduced AT1-receptor signaling limits inflammatory cytokines, osteoclast differentiation and bone resorption. |
| Vitamin K antagonists | Warfarin | Inhibit vitamin K epoxide reductase, reducing activation of vitamin K-dependent coagulation proteins. | Decrease bone quality and increase fracture risk, | Vitamin K is required for gamma-carboxylation of osteocalcin and matrix Gla protein. Inhibition may impair mineral binding in bone and alter regulation of vascular calcification. |
| Unfractionated and low-molecular-weight heparins | Unfractionated heparin; enoxaparin; dalteparin | Potentiate antithrombin and inhibit thrombin and/or factor Xa. | prolonged treatment causes bone loss | Heparin may suppress osteoblast function, enhance osteoclast-mediated resorption and alter osteoprotegerin signaling. Risk increases with longer treatment duration . |
| Direct oral anticoagulants | Apixaban; rivaroxaban; edoxaban; dabigatran | Directly inhibit factor Xa or thrombin without blocking vitamin K recycling. | Reduce fracture risk | They do not interfere with vitamin K-dependent osteocalcin carboxylation. Reduced intracranial bleeding and simpler dosing may also indirectly reduce morbidity, although falls and bleeding remain relevant. |
Interpretation note: Effects may differ by dose, treatment duration, patient age, kidney function, comorbidities and baseline fracture or cardiovascular risk. This table is an evidence summary and is not a prescribing guide.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.