
Submitted:
01 September 2026
Posted:
02 September 2026
You are already at the latest version
Abstract
This study investigates how health insurance status and the availability of healthcare professionals affect delays in care and overall health outcomes. It was hypothesized that uninsured individuals often experience longer wait times and poorer health. By exploring these interconnected factors, the research emphasizes the need for targeted policies to enhance healthcare equity and access across the state's varied communities. This study examines three research questions to identify factors influencing health care accessibility in California. Each question places a major focus on two of the variables including insurance, delays in care, health status, and healthcare professional shortages. This research uses data from the California Health Interview Survey (CHIS), which includes a sample of over 20,000 individuals, providing trends related to healthcare access across different regions. However, limitations such as small sample sizes in rural areas and the use of a digital survey collection method starting in 2022 may affect the reliability of the findings, necessitating a cautious interpretation of significant results. This study reveals how while a lack of health insurance significantly affects delays in medical care in rural areas, the association between insurance and health status is more complicated than just a simple two variable comparison. It brings attention to factors beyond coverage, such as healthcare resources and personal choices. The findings showcase the urgent need for targeted policies to enhance healthcare equity and access, ensuring timely care for all Californians, regardless of their socioeconomic status, geographic location, or level of insurance.
Keywords:
healthcare access
; health insurance status
; delays in care
; health outcomes
; healthcare professional shortage
; health equity
; health disparities
1. Introduction
The state of California serves as a home to over 39 million people. This vast population consists of both a very diverse demographic and geographic landscape. One of the drawbacks that comes with such a diverse and dispersed state in a nation without universal healthcare, is the lack of affordable healthcare for economically disadvantaged populations especially in rural regions. This multifaceted issue significantly impacts not only the health outcomes of millions of Californians but also calls the efficiency of the healthcare system into question. This study looks at the implications of health insurance status and the availability of healthcare professionals on the delay in receiving care and health status in both urban and rural areas of California.. The disparity in healthcare access for Californians can vary widely between urban and rural areas of the state. This study examines three interconnected aspects of healthcare access among Californians utilizing data from the California Health Interview Survey (CHIS) collected by the UCLA Center for Health Policy Research.
This paper first investigates the association between the lack of health insurance and the delay in care among people living in California rural counties. The primary hypothesis is that a lack of health insurance will lead to larger delays in care for all individuals whether rural or urban. Health insurance serves as the bridge to receiving medical services promptly and a lack of coverage can lead to longer wait times for necessary care or even an inability to receive that necessary care due to severely high costs. This first part of the study examines whether uninsured individuals in rural California experience longer delays in care for medical services as compared with insured individuals in these same regions and the state as a whole.
Second, the paper tests the hypothesis that health insurance coverage is a crucial factor in and determinant of the overall health status and condition of an individual. If an individual is not covered by health insurance then their ability to access care quickly and affordably will likely decrease. They will be vulnerable to health conditions and since they may not be able to access care quickly enough, their health will, on average, be poorer than those who can afford health insurance and therefore have better access to timely and affordable care. This part of the study seeks to understand whether the lack of health insurance is directly associated with lower health status among Californians and whether this relationship differs between rural and urban counties.
The final part of this study looks into how the shortage of healthcare professionals across the state of California is a crucial factor in influencing the delay in care that individuals experience. The main hypothesis is that a shortage of healthcare providers in a region leads to larger delays in care even when individuals are insured, since despite having health insurance coverage, the scarcity of healthcare professionals can render the insurance substantially less effective. This area of the study looks into how living in an area of healthcare professional shortage impacts the delay in care that Californians receive across the state as a whole.
Addressing these various issues and areas of healthcare in California, this study sheds light on how health insurance coverage, geographic location, and healthcare professional shortage collectively influence healthcare access and the health status of millions of people. It is essential to understand these relationships within the healthcare system to develop targeted policies and interventions to improve healthcare equity and access for the vast and diverse Californian communities.
2. Previous Research
The intersection of health insurance accessibility and the availability of healthcare professionals is an important area of study due to the diverse population in California and the current disparities between the state’s different regions. Initiatives such as the Affordable Care Act and Medi-Cal have taken steps towards tackling health care issues but the shortage of healthcare professionals can slow down the implementation and effectiveness of these policies. The following literature review was conducted to synthesize empirical studies and policy analyses together in order to build a comprehensive understanding of the state of health insurance coverage and healthcare professional status in California. This review was helpful in informing on the gaps in this field of research and policies that address both the accessibility of health insurance as well as the adequacy of healthcare professionals. The effects of healthcare policies, demographic shifts, and economic factors are all explored to determine their contribution to healthcare access and equality.
2.1. Health Insurance
In a study analyzing the impact of health insurance on poverty in California (Danielson et al., 2023), it was stated that health insurance enhances affordability and financial protection during health crises, which contributes to greater positive financial situations for all people. This study discusses the California Poverty Measure (CPM), a health-inclusive poverty measure, which involves both health insurance costs and needs, to display the economic stability of individuals living in poverty when faced with large health bills. It primarily focuses on individuals over the age of 65 and provides a useful tool to potentially measure the effects of future modifications to healthcare policies. For example, the expansion of Medi-Cal to all eligible income members is one change that can be tracked by the CPM to check whether it has been effective or not. Medi-Cal is a California program supported by taxes which pays for a variety of medical services for children and adults with limited income and resources.
This study found that Medi-Cal expansions under the Affordable Care Act (ACA) have significantly increased access to health insurance for millions of lower income Californians. Many of these individuals come from rural areas where healthcare is not only expensive and scarce but also sometimes of lower quality. Health insurance may not be the primary roadblock to receiving healthcare access but it does reduce the costs, thus protecting families from facing very large financial burdens after a medical emergency. The health-inclusive CPM was developed to incorporate health insurance as one of the basic human needs alongside food and shelter.
This study also conducted an analysis of health insurance and poverty . Incorporating health insurance into the poverty measure raises the resources needed to stay above the poverty line by nearly 60%. Poverty rates were much higher among uninsured Californians with 38.4% living in poverty compared to 18.5% of those with Medi-Cal eligibility and 4.2% of those with employer based coverage. Without Medi-Cal, poverty rates among young children are projected to increase from 7% to 16.9%, and 13.1% to 19.3% for adults aged 45 to 64. California residents who are not yet citizens, who are most likely to lack healthcare insurance coverage, were found to face the highest poverty rates at 27%. The anticipated 2024 expansion of Medi-Cal to all income-eligible residents could reduce poverty among non-citizens by 2.9%, benefiting undocumented immigrants and mixed-status families in particular.
The study put major emphasis on the critical contribution of Medi-Cal to basic household resources and highlighted the potential impact of California’s planned 2024 expansion of this program on poverty rates among immigrants and their families. This expansion reveals how public spending on health insurance coverage enhances the economic stability of millions of people across the state of California.
2.2. Healthcare Professional Status
In a study analyzing current programs and incentives to overcome rural physician shortages in the United States (Arredondo et al., 2023), the authors compared the various programs and incentives that have attempted to recruit physicians to areas that deal with these problems, which are mostly rural designated health professional shortage areas (HPSAs). This study maps the types and importance of these programs and incentives across the US states including California, highlighting their potential impact on addressing physician shortages and improving resource allocation in these shortage regions.
The most common programs and incentives that aim to counter these shortages involve recruiting physicians into rural areas facing significant shortages through loan repayment programs (LRPs), J-1 visa waivers, and scholarships. There are barriers, however, and each of these incentives has drawbacks such as the fact that many scholarships come with service commitments that can prevent physicians from applying for LRPs; LRPs provide a much larger financial support system for physicians than scholarships. This calls for support programs that can alleviate financial instabilities faced by rural physicians
Even though these programs are meant to increase both recruitment and retention of physicians in these rural regions, their primary focus is on recruitment, with only a small number of such incentives going towards the retention of physicians already working in rural regions. This not only accounts for the departure of a vast number of rural physicians but also a failure to replace their spots, creating a greater physician shortage issue. Most programs aim to attract new physicians; their support for existing physicians in rural areas decreases once their service commitment is completed. This study calls for an increased emphasis on retaining existing physicians in these underserved areas rather than only recruiting as they not only keep shortage numbers lower but also bring experience to the medical field in rural areas. Programs that were targeting applicants from rural backgrounds were not only found to be more likely to bring physicians to come work in these areas but also more likely retain these physicians. However, it was surprising that only a few programs favored applicants with a rural background even though there is a potentially large advantage to hiring them. A majority of incentives were offered to medical school students with only a few offering them to younger students. This study suggests that educating students on the rural physician shortage and starting residency rotations in rural areas can bring more interest in physicians to work in these areas. A large issue is that these programs are distributed unevenly by state, which results in several high need areas lacking the required incentives to solve their shortage problem. Equal allocation and targeting of these programs and incentives should be addressed to bring more healthcare professionals to all areas of need.
Despite the many ongoing efforts to address healthcare professional shortage across the country including a large shortage in California, the situation is extremely critical and could potentially worsen. This study relayed information and effects of programs and incentives that attempt to tackle this issue but their effectiveness is still in question. To fully understand which initiatives are successful in countering the shortage of healthcare professionals in HPSAs, it is essential to implement interval evaluations along with tracking recruitment and retention rates of rural physicians.
3. Methodology
3.1. Research Questions and Variables
This study focuses on three specific research questions, attempting to identify factors that result in enhanced accessibility of healthcare in California. Throughout the three research questions, we defined the variables of insurance, delay of care, health status, and healthcare professional shortages as categorical variables to simplify the analysis. The data used in the paper are from surveys conducted by the California Health Interview Survey collected by the UCLA Center for Health Policy Research, which surveyed Californians based on their geographical location (primarily the individual’s county) on, among other things, their experiences with obtaining healthcare. The California Health Interview Survey, or CHIS, randomly selects an adult respondent from a household using the next birthday. To obtain a greater diversity within the sample, CHIS conducts interviews in multiple languages including English, Spanish, Chinese, Korean, Vietnamese, and Tagalog. It contains data from a sample size of over 20,000 californians.
The third research question within the paper - studying the association between healthcare professional shortages and delay in care - used the California Government State Geoportal to study the regions and counties that were identified as shortage areas. The State Geoportal site uses government-obtained data and interviews by region to find HPSA scores, which were used to identify shortage areas within certain counties and regions.
3.2. Limitations
Limitations on the methods used to gather data for this study include small sample sizes, particularly in the rural areas, when using the CHIS dataset. Smaller sample sizes may make it more difficult to find statistically significant differences between population groups, making it harder to draw reliable conclusions from the data. This concern was addressed by combining certain geographically close rural regions to increase the sample sizes of the data, giving a further accurate picture of the conclusions.
Furthermore, recent data from the California Health Interview Survey uses The Partial Experiment Design, which may somewhat decrease the accuracy of the data, starting from 2022, because it used a digital survey collection technique. However, the trends were analyzed for multiple regions to provide greater accuracy when it came to the association between the variables over time.
Certain regions in the CHIS database had extremely low sample sizes than the survey, so much so that the data for a specific year in a region for a certain variable would be listed as unknown. To address this limitation, no conclusions were made based on unknown samples or data from the California Health Interview Survey.
3.3. Data Analysis
The data were analyzed by examining the trends of the variables with 95% confidence. In this analysis, certain variables were found to not be statistically significant. However, with variables in which data was found to be statistically significant, the conclusions and potential reasons for visible trends were highlighted to a greater extent due to a higher confidence in the results.
4. Results & Analysis
4.1. Lack of Health Insurance vs. Delay in Received Care, Adults Ages 18-65 in Rural Counties
Figure 1 shows the delay in care that has occurred over time in the state of California along with four specific rural counties. When looking at the comparison that takes place between the rural counties and California, we observe that there is a much higher delay of care that occurs within rural counties compared to the overal state. We look through varying reasons why there may be a higher delay in care within rural counties, as to the state as a whole.
Figure 1 not only looks at the comparison between rural counties and California, but how there is a change in the delay of care overtime. The overall trend of delay in receiving prescriptions or medical services has slightly decreased within the rural counties, but generally stayed similar from 2012 to 2020, especially in the state as a whole. However, from 2014 to 2016 it was evident that in both California and in the rural counties, there was a major drop in the percentage of people who were delayed in their health care. Del Norte county appears to be the county that faces the largest drop in 2016 of a delay in care. Once we move to the period between 2016 and 2018 the delay in care experienced a major increase in every rural county shown however, when looking at California as a whole, there is no major change.
Figure 2 shows the rates of uninsured people in California as well as four rural counties over a period of 8 years. Each of the rural counties had a significantly higher rate of uninsurance in 2012, and that is true for all of the years except for 2016, where they are extremely similar to the uninsurance rate of the state as a whole. When it comes to looking at the progression of uninsurance overtime, we see a slight decrease from 2012 to 2020 in each of the Rural counties, with the most significant being Yuba County. However, Yuba county also specifically saw a massive increase in the amount of people who were uninsured in 2018. We hypothesize that a possible reason for this may have been the rapid growth of the population in Yuba county in 2018, which fell the year after, indicating why the sample of the survey was also larger that year. In general, the trend of california seems to remain largely the same, with a similar proportion of people remaining uninsured each year, however, in rural counties it has seen a slight decrease, with a higher starting proportion, with occasional jumps throughout the middle.
In Figure 3, when looking at the year 2012, prior to the implementation of the major provisions of the Affordable Care Act, in California there is a great disparity when it comes to the delay in care for people who are insured versus people who are uninsured. The ones who are insured have a significantly lower delay in care compared to the ones who remain uninsured. However, in 2022 when the Affordable Care Act had been in force for years, there is not much difference between the proportion of people that are insured and uninsured when it comes to the time for receiving healthcare. We hypothesize that this rise may be linked to growing insurance coverage rates, as indicated in Figure 1, without a corresponding increase in healthcare providers. This imbalance may lead to longer wait times and increased delays for those seeking healthcare access.
When looking specifically at the rural counties, with data that is observably indifferent, there is a general trend of a decline in delay in care. This strongly correlates to the adoption and enforcement of the Affordable Care Act, which expanded medicaid and created health insurance exchanges. As a result we see a decline in delay of care for both the population that was insured as well as uninsured. However, the data remains inconclusive due overlapping confidence intervals and dropping of samples within the rural regions.
The analysis of healthcare delays in California highlights some important changes since the Affordable Care Act was implemented. While there were clear disparities between insured and uninsured individuals in 2012, by 2022, those gaps have become much smaller, indicating improved access for the uninsured. In rural areas, trends show a decrease in delays for both insured and uninsured populations since the ACA took effect, though the limited data available makes it hard to draw firm conclusions.
4.2. Lack of Health Insurance vs. Health Status, Adults Ages 18-65 in Rural and Urban Counties from 2022
Figure 4 shows the specific health status, satisfactory or unsatisfactory, of individuals who either have or don’t have insurance, in different regions in California throughout the year 2022. When Analyzing the data across various regions—both urban and rural—we find a consistent pattern: a substantial portion of the population is classified as having satisfactory health outcomes. The majority of individuals maintain a satisfactory status concerning their overall health, indicating a potential baseline of health stability across different environments.
Moreover, trends in the data suggest that insurance status does not significantly affect health outcomes. This challenges the common assumption that having insurance automatically correlates with better health, highlighting the complexity of health determinants in California.
The findings show that factors beyond insurance status and geographic location may play critical roles in influencing health outcomes. For example, healthcare resources and lifestyle choices, variables that were not surveyed or discussed, may have a substantial impact on the health outcomes of the individuals. Ultimately, this suggests that in California, neither the region in which individuals reside nor their insurance coverage guarantees improved health, pointing to a need for a more nuanced understanding of health equity and access within diverse communities. Further research is needed to explore these dynamics on the variables that may affect the disparities within health statuses.
4.3. Healthcare Professional Shortage vs. Delay in Received Care, Adults Ages 18-65 in California from 2022
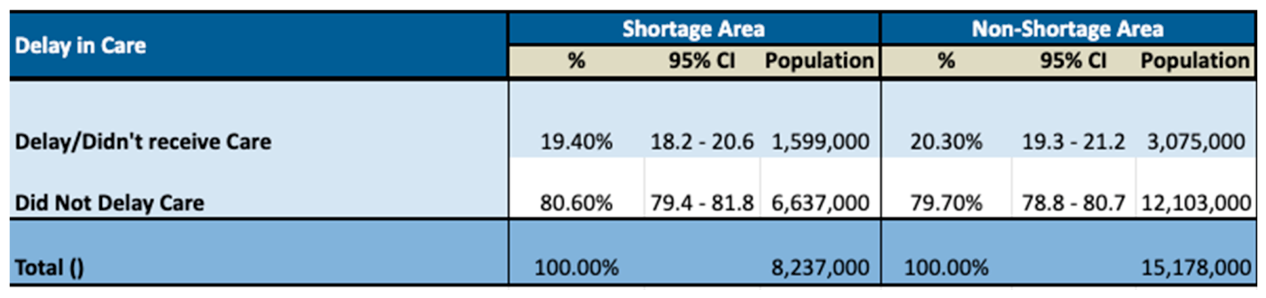
Figure 5 shows the delay in health care in areas that had a shortage of professionals and areas which did not, where there is a similar proportion of people who receive a delay in care in both areas. When examining the data on delays in care and comparing shortage versus non-shortage areas, we find no observable differences that would allow us to draw a clear relationship between these two variables. This lack of significant difference may be attributed to two potential factors.
First, areas designated as high shortage regions often receive considerable support from the National Health Service Corps. Due to their high Health Professional Shortage Area (HPSA) scores, clinicians are assigned to these regions, which helps mitigate delays in care. As a result, the performance in these shortage areas can closely align with non-shortage regions that do not face similar challenges in access to healthcare professionals.
Second, the survey data may be influenced by a behavioral trend in shortage areas. We hypothesize that many individuals in these regions may choose not to seek healthcare at all, resulting in fewer people utilizing available healthcare systems. This lower demand could mask the existence of delays, as those who do not seek care would not be counted in any delay metrics.
In general, these factors suggest that the dynamics of healthcare access are complex and ask for more investigation to fully understand the implications for health outcomes in different geographic areas, and how shortage and non-shortage areas are impacted.
5. Discussion & Conclusions
This study explored the effects of healthcare access issues in California where over 39 million people reside of which many face significant health care access challenges. It examines how health insurance status and the shortage of healthcare professionals impact delays in receiving care and overall health outcome status. This research focuses on three main aspects, the first being the relationship between a lack of health insurance and delays in receiving medical care for rural counties. The second aspect involves the relationship between a lack of health insurance and health status for rural and urban counties. Finally, the third aspect looks at the relationship between the effects of healthcare professional shortage and a delay in receiving medical care for all of California. There were numerous findings that showcase the need for creating targeted policies in order to improve healthcare equity and access for all Californians.
The first aspect of this study looked at the relationship between a lack of health insurance and delays in receiving medical care for only rural counties. The analysis of healthcare delays in rural California from 2012 to 2022 revealed multiple trends. Delays in receiving prescriptions or medical services have slightly decreased, with the most significant drop coming between 2014 to 2016. However, a sharp increase in delays occurred in rural counties in 2018. While the percentage of uninsured individuals generally declined since 2012, the counties of Trinity and Plumas saw a rise in 2018 but most rural counties returned to the decreasing trend by 2020. The disparity in care delays between insured and uninsured individuals decreased significantly post introduction of the Affordable Care Act (ACA) in 2012 which suggests improved access for the uninsured. However, an increase in delays for insured individuals from 2012 to 2022 may indicate growing insurance coverage without a proportional increase in healthcare providers, leading to longer wait times. Despite the positive trends, data limitations in rural areas prevent definitive conclusions to be made about the impact of the ACA on care delays. There are many potential reasons and inferences that could be made for the trends that were seen. First, there was major resistance towards expanding Medicaid by the Trump administration from 2017 to 2021 which may have led to increased delays in rural counties due to insufficient healthcare coverage. Second, increased health insurance coverage without a corresponding rise in healthcare providers could potentially contribute to longer wait times for insured patients, creating a large pileup of needed care. Third, the ACA appeared to have improved access for uninsured individuals, which reduced disparities in delays in care over time, although the effects of this program in rural areas remains unknown due to limited data. Fourth, since the sample sizes available and used for rural counties were small, this may obscure trends and limit the reliability of conclusions drawn about healthcare access and delays. Finally, there are a multitude of regional variations. Fluctuations in the number of uninsured individuals in specific rural counties like Trinity and Pluma could indicate varying local economic and healthcare conditions that affect overall trends.
The second aspect of this study looked at the relationship between a lack of health insurance and health status for rural and urban counties. The analysis of health status in California in 2022 revealed interesting results. A significant amount of the population reported satisfactory health, which suggests stability in health status. Interestingly, health insurance status did not appear to significantly influence these health outcomes, which challenges the idea that having health insurance actually leads to better health. This indicates that factors beyond insurance and geographic location (rural or urban) such as healthcare resources can play a crucial role in determining health. These findings show the complexity of healthcare equity and access. It emphasizes that neither region nor insurance coverage alone can ensure or even associate with improved health. Further research is necessary to explore additional variables affecting health status.
There are a variety of reasons and inferences, however, that can be attributed to these results. First, health outcomes are influenced by various factors beyond insurance, including personal lifestyle choices, environmental conditions, and access to healthcare resources. This could account for why an association was not found between health insurance and health status. Second, individuals with insurance may not necessarily have access to high quality care. This could affect health outcomes regardless of whether an individual has health insurance or not. There is a need for deeper research on this relationship. The data does suggest that there is a gap in understanding how multiple factors could possibly intersect the health of an individual, which indicates a need for more detailed research into health equity and access across diverse populations.
Finally, this study looks at the relationship between the effects of healthcare professional shortage and a delay in receiving medical care for all of California. The analysis of health status in California in 2022 revealed interesting results. The analysis of delays in care between areas with healthcare professional shortages and those without revealed no statistically significant differences, which suggest a lack of association between any of these variables. This could primarily be due to two reasons. The first is support from theNational Health Service Corps (NHSC). High shortage regions often receive additional support from the NHSC, with corps physicians getting assigned to these areas due to their Health Professional Shortage Area (HPSA) designations. This assistance helps reduce delays in care in attempts to bring levels of healthcare in shortage areas on par with non-shortage regions. Second, residents in shortage areas may opt not to seek healthcare due to personal reasons. This results in fewer individuals utilizing their accessible medical services. This lower demand could make actual delays uncertain since those not seeking care are not included in the measures of individuals experiencing great delays. There is still a need for more detailed data where the utilization of physicians and reasons behind avoiding healthcare are taken into account. Also the negative perception of many people of the quality of healthcare in certain areas, particularly rural areas, could contribute to their decision to seek care or not. This further complicates the relationship between healthcare professional shortages and delays in care.
This study puts the challenges of critical healthcare access into focus - challenges that are faced by millions of California’s diverse population - revealing how a lack of health insurance and a shortage of healthcare professionals can significantly influence delays in care and health outcomes. The findings indicate how a lack of health insurance is a notable barrier in the rural regions of this state and that the impact of this absence is a variety of health outcomes between rural and urban counties. These barriers result in worse health outcomes for millions of Californians. Additionally, the shortage of healthcare professionals highlights the need for a more efficient strategy to address disparities. The results make it clear that there is a grave urgency for targeted policies that promote equity and enhance access to healthcare for all Californians. By addressing the issues brought into focus from this study, policy makers can work towards a more inclusive healthcare system: one that ensures adequate and immediate care for everyone, regardless of their socioeconomic status, geographic location, or level of health insurance.
Acknowledgments
This project would not have been possible without the UCLA Center for Health Policy Research, which played a crucial role in collecting the data used for this study through the California Health Interview Survey (CHIS). A thank you goes out to the team at UCLA for supplying not only the data but also the analysis tools that allowed this research to be conducted effectively.
References
- The impact of health insurance on poverty in California. (2024, September 16). Public Policy Institute of California. https://www.ppic.org/publication/the-impact-of-health-insurance-on-poverty-in-california/.
- Arredondo, K., Touchett, H. N., Khan, S., Vincenti, M., & Watts, B. V. (2023). Current Programs and Incentives to Overcome rural physician shortages in the United States: A Narrative review. Journal of General Internal Medicine, 38(S3), 916–922. [CrossRef]
- Coffman, J., Fix, M., Healthforce Center at UCSF, University of California Office of the President (UC Health Division), & Physicians for a Healthy California. (2021). The state of California’s physician workforce. https://www.ucop.edu/uc-health/_files/prop-56/annunal-review-report-june2021.pdf.
- Lambe, S., Washington, D. L., Fink, A., Laouri, M., Liu, H., Fosse, J. S., Brook, R. H., & Asch, S. M. (2003). Waiting times in California’s emergency departments. Annals of Emergency Medicine, 41(1), 35–44. [CrossRef]
- New Research Reveals Long Medi-Cal Call Wait Times, Which Undermines Access to Coverage for Californians - The Children’s Partnership. (2024, September 6). The Children’s Partnership. https://www.childrenspartnership.org/news/new-research-reveals-long-medi-cal-call-wait-times-which-undermines-access-to-coverage-for-californians/.
- The impact of health insurance on poverty in California. (2024, September 16). Public Policy Institute of California. https://www.ppic.org/publication/the-impact-of-health-insurance-on-poverty-in-california/.
- Charles, S. A., Babey, S. H., & Wolstein, J. (2022). The state of health insurance in California. In UCLA Center for Health Policy Research. https://healthpolicy.ucla.edu/sites/default/files/2023-06/stateofhealthinsuranceincalifornia-report-ada-compliant-jan2022.pdf.
- California achieves lowest uninsured rate ever in 2022 - California Health Care Foundation. (2023, November 6). California Health Care Foundation. https://www.chcf.org/publication/california-achieves-lowest-uninsured-rate-ever-2022/.
- UCLA Center for Health Policy Research. (n.d.). AskCHISTM. https://healthpolicy.ucla.edu/our-work/askchis.
Figure 1.
Change in people who experience delays in care in California Rural counties, 2012-2020.
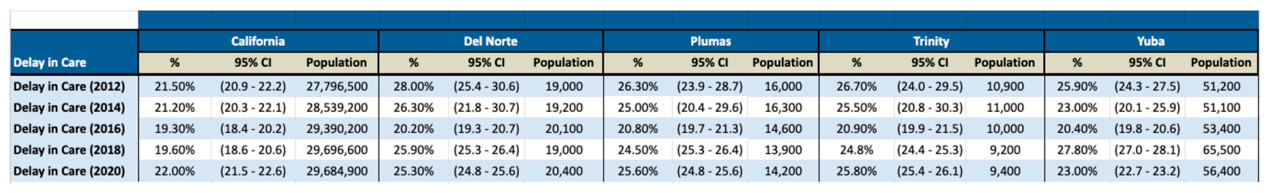
Figure 2.
Change in people uninsured in California Rural Counties overtime.
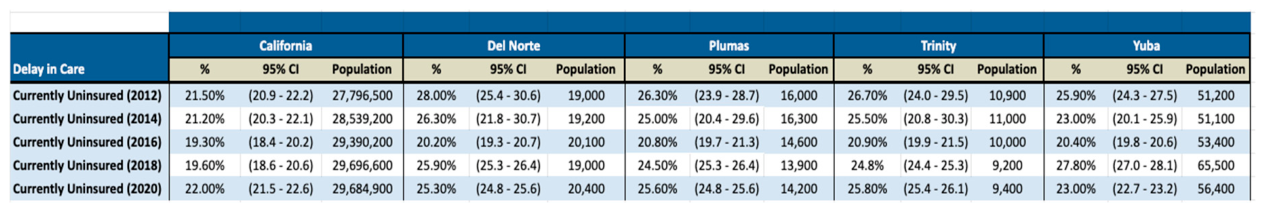
Figure 3.
Comparison of Delay in Care with Insured and Uninsured populations of California Rural Counties.
Figure 3.
Comparison of Delay in Care with Insured and Uninsured populations of California Rural Counties.
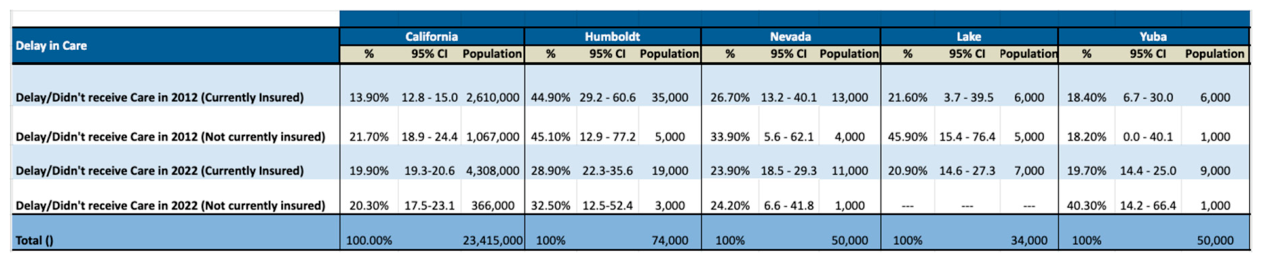
Figure 4.
Health Status of Individuals in California, Rural and Urban Areas based off insurance status. *Note In the combined version of the table, excellent, very good, good are classified as satisfactory while fair and poor are classified as unsatisfactory.
Figure 4.
Health Status of Individuals in California, Rural and Urban Areas based off insurance status. *Note In the combined version of the table, excellent, very good, good are classified as satisfactory while fair and poor are classified as unsatisfactory.
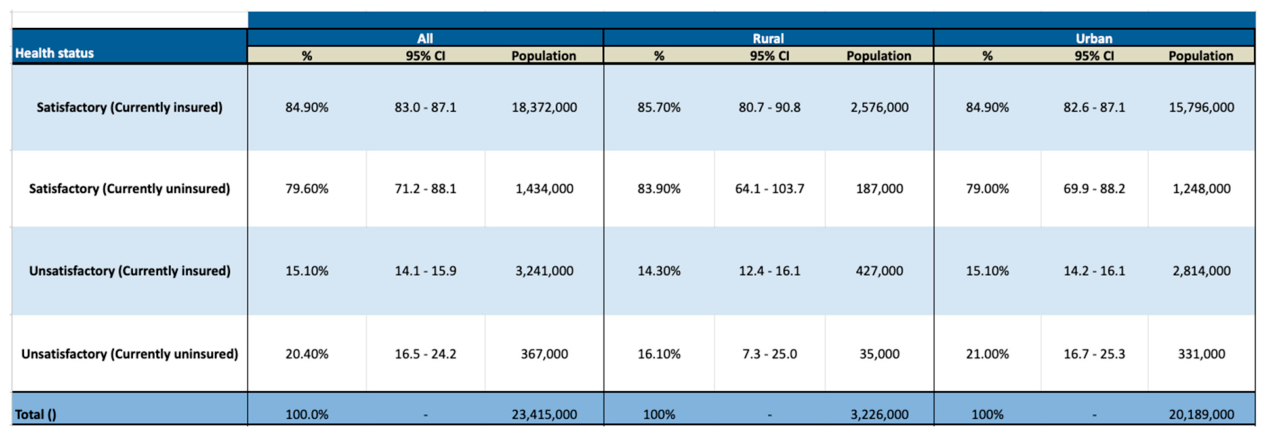
Figure 5.
Delay in Health in California Shortage Areas and Non Shortage Areas. *Note: Shortage Areas were defined as areas with an HPSA score between 21 and 25.
Figure 5.
Delay in Health in California Shortage Areas and Non Shortage Areas. *Note: Shortage Areas were defined as areas with an HPSA score between 21 and 25.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.