

Submitted:
26 August 2026
Posted:
26 August 2026
You are already at the latest version
Abstract
Endometriosis is a systemic, estrogen dependent neuroinflammatory-mediated disease affecting approximately 10-15% of women of reproductive age. Clinical manifestations include chronic pelvic pain (CPP), dysmenorrhea, dyspareunia, dyschezia, dysuria, and infertility. Endometriosis-associated pain is multifactorial and comprises overlapping nociceptive, neuropathic, and nociplastic pain phenotypes driven by persistent inflammation, neuroangiogenesis, peripheral nerve involvement, and central sensitization (CS). These mechanisms may sustain pain beyond lesion excision, highlighting the importance of pelvic nervous system (PNS) involvement. This narrative review examines the role of neuropelveology (NP) in endometriosis, focusing on pain mechanisms, diagnostic implications, and surgical decision making. NP integrates pelvic neuroanatomy and neurophysiology into structured neurological assessment, pain mapping, symptom localization, and nerve sparing surgery. Current evidence suggests that NP may complement conventional evaluation in selected patients with refractory pain, neuropathic symptoms, discordance between symptom severity and imaging findings, or suspected involvement of the sacral plexus or sciatic nerve. Recognizing distinct pain phenotypes may support individualized treatment planning by balancing lesion excision with neural preservation and identifying patients who may benefit from multidisciplinary pain management, rehabilitation, neurolysis, or neuromodulation. Although current evidence remains limited, NP should be considered a complementary framework rather than a replacement for established endometriosis management. Prospective multicenter studies using standardized diagnostic criteria and long-term functional outcomes are needed to define its clinical utility.
Keywords:
endometriosis
; neuropelveology
; chronic pelvic pain
; neuroinflammation
; pelvic nervous system
1. Introduction
Neuropelveology (NP) is an emerging interdisciplinary subspecialty dedicated to the study of pelvic neuroanatomy and neurophysiology to evaluate and manage disorders involving the pelvic nervous system (PNS) [1]. By combining anatomical, functional, and surgical perspectives, NP provides a comprehensive framework for the diagnosis and treatment of sensory, motor, and autonomic dysfunctions arising from pelvic nerve injury or disease. Growing evidence suggests NP as a promising tool in the approach and management of PNS involvement in chronic pelvic conditions. The most common pathologies involving the sacral plexus treated using NP are radiculopathies, compressions, deep infiltrating endometriosis (DIE) and tumours [1,2]. Among gynecological causes, endometriosis remains one of the most common etiologies, affecting approximately 10-15% of women of reproductive age, with 35-50% of affected individuals experiencing CPP during the course of the disease [3].
The development of NP has been largely driven by the need to better understand and manage CPP, a complex condition affecting approximately 15-26% of women worldwide and representing one of the most prevalent and debilitating gynecological diseases [3,4]. CPP is associated with a substantial reduction in quality of life, sexual function, psychological well-being, and daily functioning. The condition may arise from a wide spectrum of identifiable pelvic and extrapelvic disorders, nevertheless, in a subset of patients, no clear underlying etiology can be identified, highlighting the multifactorial nature of chronic pain syndromes [5].
Increasing evidence indicates that CPP shares pathophysiological characteristics with other chronic overlapping pain conditions, particularly alterations in central pain processing pathways [6,7]. Sustained nociceptive stimulation may induce maladaptive neuroplastic changes within the central nervous system (CNS) at both spinal and supraspinal levels, resulting in enhanced pain perception and the development of nociplastic pain. These mechanisms may contribute to the persistence, amplification, and multidimensional nature of pain observed in many patients with endometriosis, even after apparently successful treatment [4].
Traditional approaches to endometriosis have primarily focused on lesion detection, classification, and excision, often overlooking the complex interaction between the disease and the PNS [8]. Advances in the understanding of neuroimmune interactions, neural infiltration, and pain sensitization have highlighted the value of NP as a complementary framework [2]. This narrative review aims to examine the role of NP in endometriosis, with particular emphasis on pain mechanisms, improving diagnostic accuracy, and its contribution to surgical management strategies.
2. Pain Mechanisms in Endometriosis and the Neuropelveological Approach
2.1. Generalities of Endometriosis
Endometriosis is a common yet underrecognized estrogen dependent systemic disease that affects approximately 10-15% of women in reproductive age (25-45 years). The incidence increases significantly to 50% among women experiencing infertility and ranges between 35-50% in those presenting with CPP [3,9].
The disease is characterized by the growth of endometrial-like tissue, comprising endometrial glands and stroma, outside the uterine cavity. Pelvic organs are the most commonly affected sites, although it may also involve extrapelvic sites containing mesothelium, such as the pleura, peritoneum, and pericardium. This ectopic implantation is associated with systemic inflammatory responses and clinical manifestations including CPP, dyspareunia, infertility, dysmenorrhea, dyschezia, and hematochezia [9,10,11].
The etiology of endometriosis continues to be a condition whose causes and progression are not fully understood and is currently considered multifactorial, involving immune, endocrine, and inflammatory processes [12]. Sampson’s retrograde menstruation theory proposes that menstrual blood containing viable endometrial cells may reflux through patent fallopian tubes into the peritoneal cavity, implanting onto pelvic surfaces, where they proliferate, and form lesions. Even though this remains one of the most widely recognized hypotheses, it fails to sufficiently explain certain clinical presentations, such as DIE, extrapelvic endometriosis, cases reported in premenarchal girls, and in male subjects [9,12,13].
In contrast to theories centered on endometrial shedding and retrograde flow, alternative models suggest an embryological origin for ectopic tissue. Mullerianosis has been described as the presence of residual mullerian tissue within ectopic cavities resulting from aberrant migration or differentiation during embryogenesis, potentially leading to endometriosis [14. Similarly, the coelomic metaplasia theory proposes that abdominal mesothelial cells retain the capacity to transform into endometrial-like tissue in response to stimuli such as chronic inflammation [13]. This mechanism could account for the presence of lesions in anatomical regions where menstrual reflux is physiologically impossible [12,15].
Modern recent frameworks emphasize that endometriosis pathogenesis is not restricted to a single isolated mechanism, but rather results from the convergence of multiple pathways, including menstrual reflux, immune dysfunction, metaplasia, cellular migration mechanisms, and both local and systemic hormonal alterations [16]. In this context, the establishment and progression of lesions are thought to require a permissive systemic microenvironment characterized by persistent inflammation, oxidative stress, and immune dysregulation, while CPP may develop in parallel through neuroimmune mechanisms [17].
2.2. Chronic Pelvic Pain
CPP is pain perceived by the pelvic structures and is characterized by being non-malignant [18.The condition arises from a wide spectrum of pelvic and extrapelvic disorders, including hemorrhoidal disease, irritable bowel syndrome, pudendal neuropathy, sacral spinal cord injuries, vascular disorders, infections, anorectal conditions and endometriosis [5,18]. Therefore, CPP may benefit from the multidisciplinary approach offered by NP in order to provide a more comprehensive medical care [19].
Traditionally, CPP has been associated with an identifiable underlying pathology, however, pain may persist despite adequate medical management or complete surgical treatment of the primary disease. When pain persists for more than six months following adequate treatment of the presumed primary condition, it’s considered that Chronic Pelvic Pain Syndrome (CPPS) has developed [4,5].
2.2.1. Chronic Pelvic Pain in Endometriosis
Currently, conservative surgical treatment of endometriosis presents significant limitations due to the lack of complete clinical resolution in a substantial proportion of patients [7]. Endometriosis-associated pain is driven by a complex interaction between local nociceptive signaling and a sustained inflammatory microenvironment. Multiple mechanisms including peripheral, central, and cross-sensitization, lesion-specific molecular alterations, and psychosocial factors may contribute to the development and maintenance of CPP [6,18,20].
CPP establishment depends on neuroangiogenesis, a process characterized by coordinated neovascularization and sensory nerve fiber sprouting that promotes aberrant innervation of endometriotic lesions and facilitates persistent nociceptive transmission [6,18,21]. Importantly, the severity of pain correlates poorly with lesion burden or disease stage, and pain often persists or recurs following apparently complete surgical excision, highlighting the contribution of sustained neuroinflammation and central sensitization (CS) [7,20,22].
Endometriotic implants may develop throughout the pelvis and infiltrate somatic and autonomic nerves, particularly the sacral plexus and sciatic nerve, producing neuropathic pain manifestations [21,23,24]. Moreover, reports of intraneural endometriosis in the absence of peritoneal disease support perineural dissemination as an additional pathogenic mechanism [21]. The ectopic endometrial microenvironment is characterized by a sustained inflammatory milieu enriched with IL-1β, IL-6, TNF-α, prostaglandins, chemokines, NGF, and BDNF. These mediators sensitize peripheral nociceptors, promote peripheral sensitization, and establish a feed-forward inflammatory loop that perpetuates pain signaling [6]. Although ectopic endometrial lesions initially lack an organized sensory innervation, the acquisition of newly formed sensory nerve fibers through neuroangiogenesis establishes functional nociceptive pathways that sustain chronic pain transmission [20].
2.2.2. Pain Phenotypes
Endometriosis-associated pain encompasses nociceptive, neuropathic, and nociplastic mechanisms, which often coexist and contribute to the heterogeneity of symptoms observed among affected women [21,25]. Table 1.
Nociceptive pain
Neuropathic pain results from a lesion or disease affecting the somatosensory nervous system (SNS) [25]. Particularly, DEI may involve pelvic nerves directly, specifically the sacral plexus and sciatic nerve, leading to neuropathic symptoms such as radiating pain, paraesthesia, sensory disturbances, and, less frequently, motor deficits [2,23]. Evidence of intraneural endometriosis and perineural spread supports the concept that neural infiltration may represent an independent mechanism of pain generation in some patients [23]. Neuropathic pain should therefore be considered in women who present with cyclical neuropathic symptoms or pain extending beyond the pelvis [2,23].
Neuropathic pain
Neuropathic pain results from a lesion or disease affecting the somatosensory nervous system (SNS) (Gentles et al. 2024). Particularly, DEI may involve pelvic nerves directly, specifically the sacral plexus and sciatic nerve, leading to neuropathic symptoms such as radiating pain, paraesthesia, sensory disturbances, and, less frequently, motor deficits (Allahqoli et al. 2024; Siquara De Sousa et al. 2015). Evidence of intraneural endometriosis and perineural spread supports the concept that neural infiltration may represent an independent mechanism of pain generation in some patients (Siquara De Sousa et al. 2015). Neuropathic pain should therefore be considered in women who present with cyclical neuropathic symptoms or pain extending beyond the pelvis (Allahqoli et al. 2024; Siquara De Sousa et al. 2015).
Nociplastic pain
Nociplastic pain constitutes a third mechanistic category of chronic pain, distinct from nociceptive pain (caused by active tissue damage) and neuropathic pain (secondary to damage to the peripheral or central nervous system) [26]. This pain phenotype results from altered nociceptive processing despite the absence of sufficient peripheral tissue damage or a demonstrable lesion of the somatosensory nervous system to explain symptom severity [25]. CS is considered the primary mechanism underlying this condition, involving amplification of pain signalling within the CNS and enhanced responsiveness of spinal and supraspinal nociceptive pathways, which together produce pain hypersensitivity [22,25].
This alteration operates at multiple levels of the nervous system: at the peripheral level, subtle changes such as nociceptor sensitization and expansion of receptive fields may coexist; at the spinal level, spinal cord reorganization, wind-up facilitation, and glial activation have been described; and at the supraspinal level, hyperactivity and increased connectivity are observed between brain regions involved in pain and emotion processing, along with reduced activity in descending analgesic pathways. Clinically, this mechanism manifests as multifocal pain that is more intense or diffuse than would be expected given the degree of identifiable tissue or nerve damage, and is often accompanied by associated symptoms of central origin, such as fatigue, sleep disturbances, cognitive dysfunction, and hypersensitivity to sensory stimuli [26].
According to Nijs et al.. CS should be understood as a process composed of multiple mechanisms, in which there is an amplification of neural signaling within the CNS, clinically manifesting as pain hypersensitivity. This process may initially serve a protective purpose in response to tissue injury, such as surgery or an accident, and can therefore be considered a homeostatic event similar to inflammation. However, when it persists, it loses its adaptive function and becomes a maladaptive phenomenon [27]. Therefore, CS provides a framework for therapeutic approaches targeting the neurobiological mechanisms involved in pain maintenance [22,25].
In a systematic review, Zheng et al. describes how pain in endometriosis is associated with an abnormal angiogenic and neurogenic environment characterized by the proliferation of nerve fibers surrounding ectopic lesions [22]. These fibers, exposed to a persistent inflammatory microenvironment, generate sustained nociceptive stimulation that induces plastic changes in peripheral synapses. This signaling is transmitted through the dorsal horn of the spinal cord to higher central structures, including the thalamus, brainstem, and cerebral cortex, where long-term alterations in synaptic transmission and glial cell function may occur [20,22].
In this context, afferent and central pathways are amplified, generating hypersensitivity not only to painful or musculoskeletal stimuli, but also to sensory stimuli such as odors, light, sound, temperature, touch, stress, or chemical substances. Therefore, CS should not be understood solely as a pathophysiological concept, but also as a clinical tool that allows the identification of patients with persistent pain, expansion of the painful area, or symptoms disproportionate to the visible tissue damage, thereby guiding a more comprehensive assessment of chronic pain [27].
In endometriosis, persistent nociceptive input from endometriotic lesions may sustain CS, contributing to CPP despite surgical treatment and converging chronic pain syndromes [18,20,22,25]. However, it is important to acknowledge that a considerable portion of the mechanistic evidence supporting this hypothesis derives from animal models, and clinical studies in humans have been conducted in specific populations with heterogeneous methodologies. Therefore, although the CS hypothesis is biologically plausible and clinically relevant, further research is needed to fully elucidate the neurophysiological mechanisms involved and their translational implications in clinical practice [22].
2.2.4. Neural Involvement and Neuroplasticity in Endometriosis
The neuroinflammatory nature of endometriosis secondary to the dynamic of the ectopic endometrial lesions and their interactions with peripheral nerves, immune cells, and the local vascular network, ultimately promotes CPP [20]. The ectopic microenvironment is enriched with neurotrophic factors, inflammatory cytokines, prostaglandins, and estrogens that collectively drive neuroplastic changes within and surrounding endometriotic lesions. Among these mediators, NGF plays a central role in promoting sensory nerve growth, whereas macrophages represent a major source of VEGF, inflammatory cytokines, and additional neurotrophic mediators that amplify neuroimmune crosstalk and support lesion vascularization, neural remodeling, and peripheral sensitization [20,28].
Ectopic lesions actively recruit and polarize macrophages, establishing a self-perpetuating inflammatory microenvironment that promotes lesion survival, angiogenesis, and aberrant nerve fiber growth. Histological studies consistently demonstrate an increased density of small unmyelinated sensory fibers together with sympathetic and parasympathetic nerve fibers within endometriotic implants, indicating that these lesions function as active neuroimmune interfaces rather than passive ectopic tissue [20,29]. In parallel, elevated expression of NGF, brain-derived BDNF, and other neurotrophic molecules stimulates sensory nerve sprouting and nociceptor sensitization, generating hyperinnervated lesions that provide persistent nociceptive input and facilitate the transition from cyclical pain to CPP [30].
Neuroangiogenesis constitutes a pivotal mechanism linking inflammation and pain in endometriosis. Coordinated angiogenesis and sensory nerve fiber sprouting promote the establishment of functional nociceptive pathways within ectopic lesions. Once established, these newly formed sensory fibers perpetuate a positive feedback process known as neurogenic inflammation [20,31]. Activation of peripheral nociceptors induce the release of neuropeptides that recruit and activate mast cells and macrophages, resulting in sustained production of pro-inflammatory cytokines, including TNF-α and IL-1β. This reciprocal interaction continuously reinforces inflammation, neuronal sensitization, and persistent pain signaling [20,31,32,33].
Persistent peripheral nociceptive stimulation ultimately induces maladaptive plasticity within the CNS. Sustained activation of primary afferent neurons increases excitability of dorsal horn neurons, promotes synaptic remodeling and axonal sprouting, and amplifies nociceptive transmission within spinal and supraspinal pain circuits [18,20]. Consequently, CS develops, allowing pain hypersensitivity to persist even after resolution of the initial peripheral stimulus or surgical excision of lesions. This persistent neuroplastic state is considered a major mechanism underlying pain chronification and treatment resistance in women with endometriosis [18,34].
Furthermore, recent neuroimaging studies have suggested that endometriosis-associated pain may be accompanied by structural changes in brain regions involved in pain processing, anticipation, memory, and emotional modulation. Maulitz et al. found differences in gray matter volume and cortical thickness in patients with endometriosis, particularly in regions such as the cerebellum, lingual gyrus, and calcarine gyrus, supporting the hypothesis that persistent pain may be related to processes of central neuroplasticity [35].
2.3. Introduction to Neuropelveology.
NP integrates principles from neurology, gynecology, urology, colorectal surgery, and pain medicine to provide a comprehensive understanding of pelvic nerve function and pathology. The field was formally established in the early twenty-first century with the creation of the International Society of Neuropelveology by Dr. Marc Possover, with the objective of consolidating previously fragmented expertise regarding pelvic nerve disorders, their diagnostic evaluation, and therapeutic management [1]. Historically, pelvic nerves were primarily considered in the setting of surgical complications and neuropathic pain syndromes. However, only in recent years has a structured and systematic framework been developed to address the intricate functional and anatomical organization of the PNS [1].
The clinical applications of NP can be broadly categorized into four principal domains: neurological diagnosis through symptom guided localization of nerve lesions; functional assessment of somatic and autonomic pelvic pathways; surgical planning aimed at preserving neural structures and optimizing outcomes; and therapeutic interventions targeting pelvic nerve disorders through microsurgical, neuromodulatory, or rehabilitative approaches [1,5,36]. These applications have gained clinical relevance as the contribution of neural mechanisms to pelvic pain and dysfunction become better recognized [36].
The conceptual foundation of NP involves precise mapping of pelvic neural networks, clarification of their functional roles, and translation of this knowledge into clinical practice. The neurofunctional anatomy of the pelvis is defined by the complex dynamic between somatic, autonomic, and visceral components of the PNS, acknowledging the substantial overlap and bidirectional communication among these pathways [1,37]. Table 2. The clinical scope of NP extends to the management of pelvic neuropathies, lower urinary tract dysfunction, sexual dysfunction, anorectal disorders, and CCPS. In addition, it supports the development of nerve sparing surgical strategies and advances in neuromodulation therapies aimed at restoring or preserving pelvic organ function [1,37].
Somatic Innervation
Somatic innervation is predominantly mediated by the pudendal nerve, which originates from the ventral rami of S2 to S4 and provides motor and sensory supply to the perineum, external anal sphincter, and external urethral sphincter [38]. The sacral plexus, formed by contributions from the lumbosacral trunk and nerve roots S1 to S4, further supports motor and sensory innervation of the pelvic floor and portions of the lower extremities [39]. Variations in the course, branching pattern, and anatomical relationships of the pudendal nerve are clinically relevant, as they may predispose patients to entrapment syndromes or increase the risk of iatrogenic injury during pelvic surgical procedures [38,39].
Autonomic innervation
Autonomic innervation of the pelvis involves coordinated sympathetic and parasympathetic pathways. The superior hypogastric plexus, situated anterior to the aortic bifurcation and sacral promontory, gives rise to the hypogastric nerves, which descend bilaterally into the pelvis and contribute to the formation of the inferior hypogastric plexus [40,41,42]. The inferior hypogastric plexus is composed of sympathetic fibers from the hypogastric nerves, parasympathetic fibers from the pelvic splanchnic nerves arising from S2 to S4, and contributions from the sacral sympathetic trunk [40,41,42]. This plexus delivers autonomic innervation to the bladder, rectum, uterus, vagina, and other pelvic viscera, and demonstrates substantial interindividual variability in its structure and fiber distribution [40,41,42]. The presence of mixed cholinergic and adrenergic ganglia within the plexus further highlights the complexity of autonomic regulation in the pelvis [40].
Visceral Innervation
Afferent and efferent pathways from the visceral innervation system are essential for coordinated pelvic organ function. Afferent fibers convey sensory input from pelvic viscera to the CNS, whereas efferent fibers mediate motor, secretory, and vascular responses. These pathways play a central role in the regulation of urinary, anorectal, and sexual function, and their disruption may result in neuropathic pain, incontinence, or visceral dysfunction [37,41]. The small caliber and dense anatomical arrangement of pelvic nerve fibers render them particularly vulnerable to injury secondary to obstetric trauma, spinal cord lesions, or surgical interventions, with clinical manifestations that may be delayed or clinically subtle [37,41].
The clinical relevance of pelvic neuroanatomy offered by NP is particularly evident in gynecology, urology, colorectal surgery, and the multidisciplinary management of CPPS [1,2]. Detailed anatomical knowledge is fundamental for the development and application of neuroprotective surgical techniques aimed at preserving nerve integrity and minimizing postoperative functional impairment [1].
3. Implications for Diagnosis
The integration of NP into the diagnostic evaluation of endometriosis-associated pain represents a promising, but not yet universally established approach. Although it is not currently recognized as a standard diagnostic modality, growing evidence suggests that a neuropelveologic perspective may serve as a valuable complementary tool within a multidisciplinary framework, particularly in patients with complex or refractory symptoms [2,43]. Figure 1.
Endometriosis related pain is increasingly understood as a multifactorial phenomenon that extends beyond purely inflammatory or mechanical mechanisms alone. Neural infiltration, irritation, and entrapment of somatic, autonomic, and visceral pelvic nerves have been implicated in the persistence, severity, and heterogeneity of symptoms [44]. Conventional imaging modalities such as transvaginal ultrasound and magnetic resonance imaging are highly useful for detecting ovarian endometriomas and DIE. However, their ability to identify microscopic neural involvement, perineural spread, or functional nerve dysfunction remains limited [2,43]. Consequently, patients may present with severe neuropathic pain despite negative or inconclusive imaging findings [7].
A neuropelveologic assessment emphasizes the systematic evaluation of pelvic nerve pathways, including the pudendal nerve, sacral plexus, and autonomic hypogastric plexuses. Incorporating targeted neurological examination, pain mapping, and careful correlation of symptoms with known neuroanatomical distributions may enhance diagnostic precision in selected cases [1]. This approach is particularly relevant when clinical presentation suggests neuropathic characteristics such as burning pain, electric shock sensations, allodynia, or radiation along specific dermatomes [43]. This approach may also be of use in rare, but clinically significant scenarios such as isolated DIE of sacral nerve roots, where the symptoms may overlap with sciatica. Failure to detect and address such involvement may result not only in persistent severe pain, but also in progressive and potentially irreversible neural damage [45].
Furthermore, CPP in patients with suspected or confirmed endometriosis frequently overlaps with other conditions that share neuropathic or functional features. Failure to recognize these entities may contribute to persistent symptoms after standard surgical or hormonal treatment [2,43,46]. Neural involvement also influences lower back pain, lower extremity symptoms, and pain patterns that mimic orthopedic or neurological disorders, frequently delaying diagnosis and treatment [2,23]. A neuropelveologic framework encourages a broader diagnostic lens, reducing the risk of attributing all pelvic pain exclusively to endometriotic lesions [46].
The potential utility of NP becomes particularly evident in complex clinical scenarios, including recurrent pain following surgical excision, discordance between symptom severity and imaging findings, or suspicion of nerve entrapment by DIE. In such cases, a structured evaluation of pelvic neural structures may assist in refining surgical planning and avoiding incomplete treatment or unnecessary reintervention [2,43].
Despite its conceptual strengths, NP remains an evolving discipline, and high quality prospective data validating standardized diagnostic protocols are limited. Therefore, it should currently be regarded as a complementary diagnostic approach rather than a replacement for established imaging and surgical evaluation. Further research is needed to define objective diagnostic criteria, optimize patient selection, and clarify its impact on long term outcomes.
4. Surgical Decision-Making
Surgical approaches for endometriosis usually bring symptom relief and improvement of pain. However, persistent or recurrent pain after eradication surgery is frequently reported [6,46]. Prolonged nociceptive input from endometriotic lesions can remodel pain processing pathways and promote persistent hypersensitivity, contributing to CPP even after lesion removal [22]. Residual pain syndromes in these patients highlight the complexity of CPP, suggesting that lesion eradication alone may be insufficient, thus requiring more comprehensive approaches [46,47,48].
Traditional surgical planning in endometriosis is primarily lesion-oriented and anatomy-based, often without systematic consideration of pelvic neural pathways involved in pain generation [48]. Emerging evidence suggests that selected neuropelveological interventions, including neurolysis, neurectomy, and neuromodulation, may improve outcomes in carefully selected patients with neural involvement [2]. Recognizing the neuroinflammatory and neuroplastic components of endometriosis-associated pain may therefore improve diagnostic accuracy, optimize treatment selection, and support more personalized management strategies [25].
Standard surgery’s primary objective is to eradicate the macroscopically visible endometriotic tissue. Despite this, such approach does not guarantee complete disease resolution, as microscopic disease, non-resectable lesions or alternative pain mechanisms may persist, including neuropathic and centrally mediated mechanisms [46,47]. The heterogeneous nature of pain related to endometriosis highlights the need for individualized pain phenotyping and comprehensive neurological assessment. Patients often present with overlapping nociceptive, neuropathic, and nociplastic mechanisms that may respond differently to medical and surgical interventions [25]. NP offers a framework for identifying pelvic nerve dysfunction and integrating neuroanatomical, neurological, and surgical perspectives into patient care [5].
Pelvic laparoscopic surgery has become the standard treatment for endometriosis, nevertheless, postoperative pain remains a frequent and poorly characterized outcome, which may result in long-term functional morbidities [1]. High rates of pain recurrence and reoperation have been reported even after conservative or definitive surgical approaches. This issue challenges the traditional therapeutic model and highlights important gaps in the comprehensive understanding of the disease’s pathophysiology [1,46]. Orr et al. and Roman et al. reported a 23% and 44.6% of patients who underwent a second surgery after a 7-year follow-up period, respectively [7,49]. Fertility sparing surgery has been identified as a risk factor to endure recurrent pain and reintervention, suggesting that pain mechanisms beyond the endometriotic lesions themselves may be involved [7].
Alboni et al. conducted a retrospective cohort analysis in which, out of 345 patients who underwent surgery for endometriosis, 97 patients [28.1%], reported persistent post-operative pain after 3 months, despite the absence of detectable endometriotic lesions. These findings support the involvement of neural pathways in the pathophysiology of endometriosis-related pain, reinforcing the hypothesis that pain persistence may occur independently of residual or recurrent disease [46]. Understanding endometriosis as a systemic and multifactorial condition involving nociceptive, neuropathic, and neuroplastic pain mechanisms is essential to reduce long-term morbidity and offer patients a better quality of life [1].
Becker et al. analyzed pain recurrence after endometriosis treatment in a systematic review including 3,198 patients who underwent surgery followed by medical therapy between 1992 and 2014. A median of 31% of patients reported persistent pain at the end of medical treatment, leading authors to suggest that surgical factors, such as adhesions or nerve-related injury, may contribute to postoperative pain persistence [50]. In this context, surgical decision-making must balance lesion resection against neural preservation, particularly in cases where pain patterns suggest neuropathic involvement.
The weak correlation between disease extent and pain severity supports the role of sustained neuroinflammatory and neuroplastic changes that maintain pain independently of lesion size or activity [20] A study by Orr et al. suggests that endometriosis-related pain has a CS component, characterized by sustained hyperexcitability of the central nociceptive system, which can amplify and perpetuate pain perception even after adequate medical or surgical treatment. The authors used the CSI to assess pain perception before and after endometriosis surgery. Higher baseline CSI scores were associated with increased pain severity at postoperative follow-up, despite surgical intervention. Furthermore, patients with multiple chronic overlapping pain conditions, such as fibromyalgia, chronic fatigue syndrome, or migraine, exhibited significantly higher CSI scores after surgery and poorer pain outcomes compared to patients without these comorbidities [7].
Together, these findings underscore the limitations and potential functional consequences of standard surgical approaches in endometriosis-related CPP [1,50]. Extensive laparoscopic pelvic surgery may result in unrecognized nerve injury, contributing to persistent postoperative pain and functional impairment. Consequently, patients are often managed with neuromodulatory or symptomatic treatments without addressing the underlying neural mechanisms of pain. This highlights the importance of a detailed understanding of pelvic nerve anatomy and function, forming the basis of NP, whose objective is to identify, preserve, and, when necessary, appropriately manage pelvic neural structures during surgical interventions [1].
5. Discussion
The present review highlights the potential of NP as both a diagnostic framework and a therapeutic strategy for pain management in patients with endometriosis. In this manner, current evidence suggests that NP may serve as a bridge between traditional gynecological assessment, and modern multidisciplinary approaches with a special focus on the understanding of complex pain in endometriosis. The reviewed evidence suggests that a neuropelveological evaluation may facilitate the identification of neuropathic and nociplastic pain mechanisms that frequently remain undetected when using conventional diagnostic approaches. Furthermore, the available evidence supports the concept of endometriosis as a neuroinflammatory condition where neural remodeling and inflammatory mechanisms contribute to persistent pain. The neurobiological perspective reinforces the need to assess patients considering the pain mechanisms surrounding the pathology and integrating them into a routine clinical practice. Additionally, persistent or recurrent pain following conventional treatment when using an excision-based management may lead to repeated interventions as a consequence of residual disease or recurrence of endometriosis. However, the reviewed evidence indicates that in many cases the persistence of pain after medical or surgical management may also reflect peripheral nerve involvement, CS, or nociplastic pain mechanisms [6,44,48,50]. Within this context, NP provides a comprehensive framework that integrates these mechanisms into the assessment and management of endometriosis-associated pain [1,17,51].
A key finding of this review is that the persistence or recurrence of pain following apparently successful surgical treatment reinforces the concept that endometriosis-associated pain cannot be explained solely by the presence or extent of ectopic lesions [5]. This challenges the traditional assumption that endometriosis symptom resolution depends on the complete excision. Consistent with this perspective, accumulating evidence from studies by Alboni et al., Song et al. and Golińska et al. suggest that pain in endometriosis also involves peripheral nerve alterations, neuroimmune interactions, central and peripheral sensitization, all of which may contribute to pain chronification and symptom persistence despite lesion excision [6,33,46].
In this way, the comparison of a series of studies concerning the evaluation of CPP reveals a pattern regarding the presence of persistent pain after medical or surgical management, which should not be interpreted as treatment failure, incomplete resection, or residual disease. Becker et al. noted that the response to medical treatment is heterogeneous and that a significant percentage of patients continue to experience pain despite the use of hormonal therapies [50]. Similarly, various studies have shown that symptoms such as pelvic pain, dysmenorrhea, and dyspareunia may persist or recur even after a technically adequate excision [20,33,45,46,49,50]. In this context, Orr et al. demonstrated that high preoperative CSI scores were associated with worse pain outcomes following surgery for endometriosis, suggesting that CS is a key factor in the approach of these patients and the need to develop standardized tools for managing CS. [7].
Furthermore, the neuroimaging findings described by Maulitz et al. support the present perspective by identifying structural changes in the brain of patients with endometriosis, suggesting that recurrent visceral pain may be associated with central neuroplasticity processes [35]. The study also emphasizes that the pain experience in endometriosis does not depend exclusively on peripheral pathophysiological mechanisms, but also on central processes related to pain perception, the emotional relationship to pain, and neuroplastic changes associated with chronic pain [35]. Taken together, these findings indicate that persistent pain following conventional treatment may reflect a heterogeneous pain phenotype, in which nociceptive, neuropathic, nociplastic, neuroimmune, and central mechanisms interact [18,25,44]. Consequently, NP recognizes the different pain mechanisms, expanding the traditional paradigm of management by incorporating detailed neuropelvic anatomy, assessment, and imaging into clinical decision making. This approach facilitates the identification of patients who may benefit from surgery or medical treatment alone and those who may require a more comprehensive approach targeting the individual underlying pain mechanisms.
Moreover, the growing recognition of NP is reflected in the recent publication of the first ISON guidelines, which represent the first attempt to standardize the diagnosis and surgical treatment of endometriosis involving sciatic nerve and sacral plexus. These recommendations emphasize the importance of a structured neuropelveological history, neurological examination, functional assessment and a thorough surgical planning. Although these recommendations focus on DIE and remain largely based on expert consensus in specialized centers they constitute the first international framework to standardize terminology, diagnostic criteria, surgical approaches, and rehabilitation, laying the groundwork for the integration of neuropelveological care into routine clinical practice and for future multicenter studies across diverse healthcare settings [52].
In this regard, pain associated with endometriosis should be understood as a multidimensional experience in which biological, cognitive, and affective components interact. Therefore, procedures aimed exclusively at hormonal suppression, pain management or the resection surgery may not be effective in patients who already exhibit changes related to nociplasticity. Recognizing this distinction is clinically important, as it can help prevent medical overtreatment and surgical reintervention. It can also facilitate earlier referral to multidisciplinary pain management, including pelvic floor rehabilitation, psychological support, and neuropelvic evaluation when neural involvement is suspected [1,2]. Ultimately, integrating NP into routine clinical practice may contribute to a more precise phenotyping of endometriosis-associated pain and improvement of patient care.
6. Limitations and Future Perspectives
As previously mentioned, the neuropelveologic approach in endometriosis represents a relatively novel therapeutic strategy and, as such, is associated with several limitations. These include the considerable heterogeneity across studies in study design, surgical techniques, and reported outcomes. Additionally, there remains a paucity of evidence evaluating long-term efficacy and providing a broader perspective on outcomes, including pain, pain recurrence, long-term follow-up, and functional outcomes [2].
The available literature on NP in endometriosis remains insufficient and is largely based on observational studies, retrospective cohorts, case series, the majority in specialized centers. Allahqoli et al. identified only six studies reporting the efficacy of various neuromodulation techniques in managing endometriosis-related symptoms. Although these findings appear promising, further research is required to more comprehensively establish the benefits and limitations of these approaches [2]. In this way, despite the emergence of novel neuropelveological techniques, the currently available evidence remains limited.
Overall, pelvic nerve pathologies, including endometriosis, are frequently misdiagnosed and underestimated due to limited awareness regarding the existence and the underreporting of such conditions. Several factors may contribute to their underrepresentation in clinical practice, including the anatomical complexity of the PNS and the restricted accessibility of pelvic nerves for neurophysiological assessment and neurosurgical interventions. Furthermore, pain is inherently subjective, and despite the availability of validated pain assessment scales, no objective method currently exists to comprehensively characterize or quantify pain in patients with endometriosis. Consequently, discrepancy between symptom perception and disease burden may contribute to a delayed diagnosis, with many patients being identified only after the disease has progressed to more advanced stages [1].
Furthermore, adequate training in surgical techniques is essential to reduce procedural variability and enhance the consistency and reliability of clinical outcomes [46,53]. Additionally, most available data stems from highly specialized centers with extensive experience in retroperitoneal pelvic neuroanatomy and neurofunctional surgery, which limits the reproducibility across centers. This highlights the need for specialized training and adequate infrastructure. Many centers, especially in low and middle-income countries, may lack advanced laparoscopic and neuromodulation equipment required to perform this type of procedure. As a result, NP faces several challenges, including specialized training, surgical complexity, access to surgical technologies, and the economic burden on patients associated with this type of care [52].
A 2024 study by Gentles et al. highlighted that, although several tools are currently available to identify CS and nociplastic pain in patients with endometriosis, including semi-objective clinical assessments evaluating pelvic sensitivity, myofascial trigger points, allodynia, hyperalgesia, and pelvic floor pain, these methods have not yet been universally standardized or validated. As a result, accurately characterizing pain mechanisms, stratifying patients, and comparing findings across studies remains challenging. The authors therefore emphasize the need to develop and validate a comprehensive set of diagnostic tools, including neurophysiological assessments, biomarkers, and neuroimaging technique to enable accurate identification and stratification of pain mechanisms CS in individuals with endometriosis [25]. Standardized and validated assessment methods would not only enhance the reproducibility of research findings but also facilitate their integration into routine clinical practice [7,25]
Despite the clinical potential of NP, several important considerations should be acknowledged. Recently, the ISON guidelines were published, they summarize the current concepts regarding the diagnosis, pathophysiology, and surgical management of endometriosis of the sacral plexus and sciatic nerve. Although the recent publication of said guidelines represents an important step toward the standardization of NP in endometriosis, studies show high heterogeneity in their design, populations, surgical techniques, and outcomes which also restricts direct comparisons between studies [52]. Therefore, the findings presented in this review should be interpreted within the context of these limitations. Studies should focus on validating current diagnostic criteria, surgical indications, long-term outcomes, accessibility and cost-effectiveness in order to be translated across clinical settings. In parallel, advances in artificial intelligence and precision medicine support the idea of multidisciplinary medical management to optimize the stratification of patients, prediction in treatment response and personalized management and rehabilitation. Although these approaches are novel to the field they represent a promising direction to translate neuropelveological concepts into standardized clinical practice [54]. Future prospective guidelines call for multicenter studies with standardized diagnostic criteria and outcome measures to define the role of NP in the management of endometriosis.
7. Conclusion
NP represents a significant conceptual shift in our understanding of pain associated with endometriosis, as it incorporates the role of the peripheral nervous system and subsequent mechanisms of central pain sensitization in the pathophysiology of this disease. The available evidence suggests that pain associated with endometriosis goes beyond the mere presence of ectopic lesions and is due to interactions involving inflammatory, neuroimmunological, and neuroplastic processes that explain the persistence of symptoms even after hormonal or surgical treatment.
Although NP remains an emerging field and current evidence is limited, its integration as a complement to the conventional approach could improve the characterization of different pain phenotypes, optimizing treatment planning by identifying patients who might benefit from specific interventions, such as neuromodulation or neurolysis procedures.
Furthermore, before considering the systematic incorporation of these strategies into clinical practice, well-structured prospective studies are needed to help define therapeutic indications, evaluate long-term functional outcomes, and determine their cost-effectiveness.
In total, NP should not be considered a substitute for current endometriosis treatment, but rather a complementary conceptual and clinical framework that reinforces a multidisciplinary and individualized therapeutic approach based on the possible pain mechanisms involved, with the potential to improve diagnostic accuracy, surgical decision-making, and patients’ quality of life.
Author Contributions
Conceptualization, G.C.H. and F.E.S.; methodology, G.C.H. and E.C.L.L.; software, M.F.B.G. AND T.M.G.; validation, R.C.C., A.G.S.B. and D.C.O.; formal analysis, D.D.V.; investigation, X.A.V and E.S.A.; resources, R.C.C. and A.G.S.B; data curation, E.C.L.L, F.E.S and G.C.H..; writing—original draft preparation, G.C.H., M.F.B.G.; writing—review and editing, G.C.H., E.C.L.L., M.F.B.G, P.C.M.P., and L.M.G..; visualization, G.C.H.; supervision, F.E.S, G.C.H., R.C.C and A.G.S.B.; project administration, F.E.S..; funding acquisition, R.C.C., A.G.S.B. and D.C.O. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| NP | Nuropelveology |
| PNS | Pelvic nervous system |
| CPP | Chronic pelvic pain |
| CSI | Central Sensibization Inventory |
| DIE | Deep infiltrating endometriosis |
| CNS | Central nervous system |
| CPPS | Chronic pelvic pain syndrome |
| CS | Central sensitization |
References
- Abramiuk, Monika; Grywalska, Ewelina; Małkowska, Paulina; Sierawska, Olga; Hrynkiewicz, Rafał; Niedźwiedzka-Rystwej, Paulina. The Role of the Immune System in the Development of Endometriosis. Cells 2022, 11(13), 2028. [Google Scholar] [CrossRef] [PubMed]
- Alboni, Carlo; Melegari, Simona; Mattos, Ludovica Camacho; Farulla, Antonino. Effects of Osteopathic Manipulative Therapy on Recurrent Pelvic Pain and Dyspareunia in Women after Surgery for Endometriosis: A Retrospective Study. Minerva Obstet. Gynecol. 2024, 76(3). [Google Scholar] [CrossRef] [PubMed]
- Allahqoli, Leila; Hakimi, Sevil; Momenimovahed, Zohre; et al. Neuropelveology for Endometriosis Management: A Systematic Review and Multilevel Meta-Analysis. J. Clin. Med. 2024, 13(16), 4676. [Google Scholar] [CrossRef] [PubMed]
- Andres, Marina Paula; Rufino, Clarisse da Costa; Krishnan, Ramanathan Anantharama; Jain, Sidharth; Gomes, Bruno Duarte; Abrao, Mauricio S. Machine Learning Models for Non-Invasive Endometriosis Triage Using a Laparoscopically and Histologically Verified Cohort. Eur. J. Obstet. Gynecol. Reprod. Biol. 2026, 324(115237), 115237. [Google Scholar] [CrossRef] [PubMed]
- As-Sanie, Sawsan; Harris, Richard E.; Napadow, Vitaly; et al. Changes in Regional Gray Matter Volume in Women with Chronic Pelvic Pain: A Voxel-Based Morphometry Study. Pain 2012, 153(5), 1006–1014. [Google Scholar] [CrossRef] [PubMed]
- As-Sanie, Sawsan; Ross, Whitney T.; Till, Sara R. Evaluation and Treatment of Chronic Pelvic Pain. Obstet. Gynecol. 2026, 147(1), 21–43. [Google Scholar] [CrossRef] [PubMed]
- Aurore, Valerie; Röthlisberger, Raphael; Boemke, Nane; et al. Anatomy of the Female Pelvic Nerves: A Macroscopic Study of the Hypogastric Plexus and Their Relations and Variations. J. Anat. 2020, 237(3), 487–494. [Google Scholar] [CrossRef] [PubMed]
- Becker, Christian M.; Gattrell, William T.; Gude, Kerstin; Singh, Sukhbir S. Reevaluating Response and Failure of Medical Treatment of Endometriosis: A Systematic Review. Fertil. Steril. 2017, 108(1), 125–136. [Google Scholar] [CrossRef] [PubMed]
- Borghese, B.; Santulli, P.; Streuli, I.; Lafay-Pillet, M.-C.; de Ziegler, D.; Chapron, C. Récidive de la douleur après chirurgie pour endométriose profonde: pourquoi ? Que faire ? J. De Gynecol. Obstet. Et. Biol. De La Reprod. 2014, 43(1), 12–18. [Google Scholar] [CrossRef] [PubMed]
- Cano-Herrera, Gabriela; Nehmad, Sylvia Salmun; Gascón, Jimena Ruiz de Chávez; et al. Endometriosis: A Comprehensive Analysis of the Pathophysiology, Treatment, and Nutritional Aspects, and Its Repercussions on the Quality of Life of Patients. Biomedicines 2024, 12(7), 1476. [Google Scholar] [CrossRef] [PubMed]
- Chen, Liang-Hsuan; Lo, Wei-Che; Huang, Hong-Yuan; Wu, Hsien-Ming. A Lifelong Impact on Endometriosis: Pathophysiology and Pharmacological Treatment. Int. J. Mol. Sci. 2023, 24(8), 7503. [Google Scholar] [CrossRef] [PubMed]
- Chen, Yixiao; Li, Tian. Unveiling the Mechanisms of Pain in Endometriosis: Comprehensive Analysis of Inflammatory Sensitization and Therapeutic Potential. Int. J. Mol. Sci. 2025, 26(4), 1770. [Google Scholar] [CrossRef] [PubMed]
- Cho, Young Sam. Chronic Pelvic Pain and Neuropelveology. Int. Neurourol. J. 2017, 21(4), 233–234. [Google Scholar] [CrossRef] [PubMed]
- Clavien, Pierre A.; Barkun, Jeffrey; de Oliveira, Michelle L.; et al. The Clavien-Dindo Classification of Surgical Complications: Five-Year Experience: Five-Year Experience. Ann. Surg. 2009, 250(2), 187–196. [Google Scholar] [CrossRef] [PubMed]
- Fitzcharles, Mary-Ann; Cohen, Steven P.; Clauw, Daniel J.; Littlejohn, Geoffrey; Usui, Chie; Häuser, Winfried. Nociplastic Pain: Towards an Understanding of Prevalent Pain Conditions. Lancet 2021, 397(10289), 2098–2110. [Google Scholar] [CrossRef] [PubMed]
- França, Patricia Ribeiro de Carvalho; Lontra, Anna Carolina Pereira; Fernandes, Patricia Dias. Endometriosis: A Disease with Few Direct Treatment Options. Molecules 2022, 27(13), 4034. [Google Scholar] [CrossRef] [PubMed]
- Gentles, Avonae; Goodwin, Emma; Bedaiwy, Yomna; Marshall, Nisha; Yong, Paul J. Nociplastic Pain in Endometriosis: A Scoping Review. J. Clin. Med. 2024, 13(24), 7521. [Google Scholar] [CrossRef] [PubMed]
- Giudice, Linda C.; Oskotsky, Tomiko T.; Falako, Simileoluwa; Opoku-Anane, Jessica; Sirota, Marina. Endometriosis in the Era of Precision Medicine and Impact on Sexual and Reproductive Health across the Lifespan and in Diverse Populations. FASEB J. Off. Publ. Fed. Am. Soc. Exp. Biol. 2023, 37(9). [Google Scholar] [CrossRef] [PubMed]
- Golinska, Monika; Wołyniak, Maria; Kulesza, Piotr; Fendler, Wojciech. Neuroinflammation Is Responsible for Pain in Endometriosis - Targeting the JAK-STAT Pathway and Mast Cell Activation. Front. Immunol. 2025, 16, 1621178. [Google Scholar] [CrossRef] [PubMed]
- ISON. ISON. 21 May 2026. Available online: https://www.theison.org/ison-guidelines/.
- Kondo, William; Leite, Guilherme Karam Corrêa; Fernandes, Rodrigo; et al. Useful Pelvic Retroperitoneal Neuroanatomy for Benign Gynecologic Surgery: A Cadaveric Dissection. J. Minim. Invasive Gynecol. 2021, 28(1), 20–21. [Google Scholar] [CrossRef] [PubMed]
- Kot, Aleksandra; Abramek, Kacper; Sobczak, Fryderyk; et al. Morphology, Topography, and Composition of the Inferior Hypogastric Plexuses and Hypogastric Nerves: A Combined Anatomical, Histological and Immunohistochemical Study on 50 Human Cadavers. Clin. Anat. 2026, no. ca.70090. [Google Scholar] [CrossRef] [PubMed]
- Lamceva, Jelizaveta; Uljanovs, Romans; Strumfa, Ilze. The Main Theories on the Pathogenesis of Endometriosis. Int. J. Mol. Sci. 2023, 24(5), 4254. [Google Scholar] [CrossRef] [PubMed]
- Liu, Danqiu; Liu, Minjie; Yu, Pinling; Li, Hongfeng. Brain-Derived Neurotrophic Factor and Nerve Growth Factor Expression in Endometriosis: A Systematic Review and Meta-Analysis. Taiwan. J. Obstet. Gynecol. 2023, 62(5), 634–639. [Google Scholar] [CrossRef] [PubMed]
- Maddern, Jessica; Grundy, Luke; Castro, Joel; Brierley, Stuart M. Pain in Endometriosis. Front. Cell. Neurosci. 2020, 14, 590823. [Google Scholar] [CrossRef] [PubMed]
- Mariadas, Heidi; Chen, Jie-Hong; Chen, Kuo-Hu. The Molecular and Cellular Mechanisms of Endometriosis: From Basic Pathophysiology to Clinical Implications. Int. J. Mol. Sci. 2025, 26(6), 2458. [Google Scholar] [CrossRef] [PubMed]
- Masferrer-Ferragutcasas, Carina; Delgado-Gil, Raquel; Colas, Eva. Rethinking Endometriosis Recurrence: From Clinical Challenge to Biological Opportunity. npj Women’s Health 2026, 4(1). [Google Scholar] [CrossRef]
- Maulitz, L.; Nehls, S.; Stickeler, E.; et al. Psychological Characteristics and Structural Brain Changes in Women with Endometriosis and Endometriosis-Independent Chronic Pelvic Pain. Hum. Reprod. 2024, 39(11), 2473–2484. [Google Scholar] [CrossRef] [PubMed]
- McNamara, Helen C.; Frawley, Helena C.; Donoghue, Jacqueline F.; et al. Peripheral, Central, and Cross Sensitization in Endometriosis-Associated Pain and Comorbid Pain Syndromes. Front. Reprod. Health 2021, 3 (September), 729642. [Google Scholar] [CrossRef] [PubMed]
- Medina, Melissa G.; Lebovic, Dan I. Endometriosis-Associated Nerve Fibers and Pain. Acta Obstet. Et. Gynecol. Scand. 2009, 88(9), 968–975. [Google Scholar] [CrossRef] [PubMed]
- Moradi, Yousef; Shams-Beyranvand, Mehran; Khateri, Sorour; et al. A Systematic Review on the Prevalence of Endometriosis in Women. Indian J. Med. Res. 2021, 154(3), 446–454. [Google Scholar] [CrossRef] [PubMed]
- Morotti, Matteo; Vincent, Katy; Brawn, Jennifer; Zondervan, Krina T.; Becker, Christian M. Peripheral Changes in Endometriosis-Associated Pain. Hum. Reprod. Update 2014, 20(5), 717–736. [Google Scholar] [CrossRef] [PubMed]
- Morotti, M.; Vincent, K.; Becker, C. M. Mechanisms of Pain in Endometriosis. Eur. J. Obstet. Gynecol. Reprod. Biol. 2017, 209, 8–13. [Google Scholar] [CrossRef] [PubMed]
- Mozafarpour, Sarah; Chen, Annie; Mogica, Jan Alberto Paredes; et al. Urodynamic Autonomic Bladder Dysfunction in Women with Complex Chronic Pelvic Pain Is Associated with Small Fiber Polyneuropathy. Neurourol. Urodyn. 2022, 41(1), 482–489. [Google Scholar] [CrossRef] [PubMed]
- Nijs, Jo; Malfliet, Anneleen; Nishigami, Tomohiko. Nociplastic Pain and Central Sensitization in Patients with Chronic Pain Conditions: A Terminology Update for Clinicians. Braz. J. Phys. Ther. 2023, 27(3), 100518. [Google Scholar] [CrossRef] [PubMed]
- on behalf of the PRE-EMPT trial collaborative group; Middleton, Lee J.; Daniels, Jane P.; Weckesser, Annalise; Bhattacharya, Siladitya. Preventing Recurrence of Endometriosis by Means of Long-Acting Progestogen Therapy (PRE-EMPT): Report of an Internal Pilot, Multi-Arm, Randomised Controlled Trial Incorporating Flexible Entry Design and Adaption of Design Based on Feasibility of Recruitment. Trials 2017, 18(1). [Google Scholar] [CrossRef] [PubMed]
- Orr, Natasha L.; Huang, Alice J.; Liu, Yang Doris; et al. Association of Central Sensitization Inventory Scores with Pain Outcomes after Endometriosis Surgery. JAMA Netw. Open 2023, 6(2), e230780. [Google Scholar] [CrossRef] [PubMed]
- Pašalić, Elma; Tambuwala, Murtaza M.; Hromić-Jahjefendić, Altijana. Endometriosis: Classification, Pathophysiology, and Treatment Options. Pathol. Res. Pract. 2023, 251(154847), 154847. [Google Scholar] [CrossRef] [PubMed]
- Possover, Marc. Neuropelveology: An Emerging Discipline for the Management of Pelvic Neuropathies and Bladder Dysfunctions through to Spinal Cord Injury, Anti-Ageing and the Mars Mission. J. Clin. Med. 2020, 9(10), E3285. [Google Scholar] [CrossRef] [PubMed]
- Possover, Marc; Andersson, Karl-Erik; Forman, Axel. Neuropelveology: An Emerging Discipline for the Management of Chronic Pelvic Pain. Int. Neurourol. J. 2017, 21(4), 243–246. [Google Scholar] [CrossRef] [PubMed]
- Possover, Marc; Forman, Axel; Rabischong, Benoit; Lemos, Nucelio; Chiantera, Vito. Neuropelveology: New Groundbreaking Discipline in Medicine. J. Minim. Invasive Gynecol. 2015, 22(7), 1140–1141. [Google Scholar] [CrossRef] [PubMed]
- Ripperda, Christopher M.; Jackson, Lindsey A.; Phelan, John N.; Carrick, Kelley S.; Corton, Marlene M. Anatomic Relationships of the Pelvic Autonomic Nervous System in Female Cadavers: Clinical Applications to Pelvic Surgery. Am. J. Obstet. Gynecol. 2017, 216(4), 388.e1–388.e7. [Google Scholar] [CrossRef] [PubMed]
- Roman, Horace; Chanavaz-Lacheray, Isabella; Hennetier, Clotilde; et al. Long-Term Risk of Repeated Surgeries in Women Managed for Endometriosis: A 1,092 Patient-Series. Fertil. Steril. 2023, 120(4), 870–879. [Google Scholar] [CrossRef] [PubMed]
- Signorile, Pietro G.; Baldi, Feliciano; Bussani, Rossana; D’Armiento, Mariarosaria; De Falco, Maria; Baldi, Alfonso. Ectopic Endometrium in Human Foetuses Is a Common Event and Sustains the Theory of Müllerianosis in the Pathogenesis of Endometriosis, a Disease That Predisposes to Cancer. J. Exp. Clin. Cancer Res. 2009, CR 28(1). [Google Scholar] [CrossRef] [PubMed]
- De Sousa, Siquara; C., Ana; Capek, Stepan; Amrami, Kimberly K.; Spinner, Robert J. Neural Involvement in Endometriosis: Review of Anatomic Distribution and Mechanisms. Clin. Anat. 2015, 28(8), 1029–1038. [Google Scholar] [CrossRef] [PubMed]
- Smolarz, Beata; Szyłło, Krzysztof; Romanowicz, Hanna. Endometriosis: Epidemiology, Classification, Pathogenesis, Treatment and Genetics (review of Literature). Int. J. Mol. Sci. 2021, 22(19), 10554. [Google Scholar] [CrossRef] [PubMed]
- Song, Soo Youn; Jung, Ye Won; Shin, Wonkyo; et al. Endometriosis-Related Chronic Pelvic Pain. Biomedicines 2023, 11(10), 2868. [Google Scholar] [CrossRef] [PubMed]
- Thiel, P.; Kobylianskii, A.; Mcgrattan, M.; Lemos, N. Entrapped by Pain: The Diagnosis and Management of Endometriosis Affecting Somatic Nerves. In Best Practice and Research Clinical Obstetrics and Gynaecology; 2024. [Google Scholar]
- Triolo, Onofrio; Laganà, Antonio Simone; Sturlese, Emanuele. Chronic Pelvic Pain in Endometriosis: An Overview. J. Clin. Med. Res. 2013, 5(3), 153–163. [Google Scholar] [CrossRef] [PubMed]
- Vercellini, Paolo; Salmeri, Noemi; Bandini, Veronica; et al. Medical Treatment for Endometriosis: One Size Does Not Fit All. J. Clin. Med. 2026, 15(6), 2408. [Google Scholar] [CrossRef] [PubMed]
- Woolf, Clifford J. Central Sensitization: Implications for the Diagnosis and Treatment of Pain. Pain 2011, 152(3), S2–S15. [Google Scholar] [CrossRef] [PubMed]
- Wu, Jinjie; Xie, Hongyu; Yao, Shuzhong; Liang, Yanchun. Macrophage and Nerve Interaction in Endometriosis. J. Neuroinflammation 2017, 14(1). [Google Scholar] [CrossRef] [PubMed]
- Yan, Yun; Inal, Busra; Kapavarapu, Prasanna; Alber, Keri; Rao, Satish S. C. Novel Concepts on the Functional Neuroanatomy of the Anorectum: Implications for Anorectal Neuropathy and Neuromodulation Therapy. Am. J. Gastroenterol. 2024, 120(7), 1478–1487. [Google Scholar] [CrossRef] [PubMed]
- Zamurovic, Milena; Tomic, Ana; Djordjevic, Katarina; et al. Isolated Deep Infiltrating Endometriosis of the Sciatic Nerve: A Case Report and Overview of the Literature. Medicina 2023, 59(12), 2161. [Google Scholar] [CrossRef] [PubMed]
- Zapletal, J.; Nanka, O.; Halaska, M. J. Anatomy of the Pudendal Nerve in Clinically Important Areas: A Pictorial Essay and Narrative Review. In Surgical and Radiologic Anatomy; 2024. [Google Scholar]
- Zheng, Ping; Zhang, Wen; Leng, Jinhua; Lang, Jinghe. Research on Central Sensitization of Endometriosis-Associated Pain: A Systematic Review of the Literature. J. Pain Res. 2019, 12 (May), 1447–1456. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
From lesion-centered management to a neuropelveological framework for endometriosis-associated pain.
Figure 1.
From lesion-centered management to a neuropelveological framework for endometriosis-associated pain.
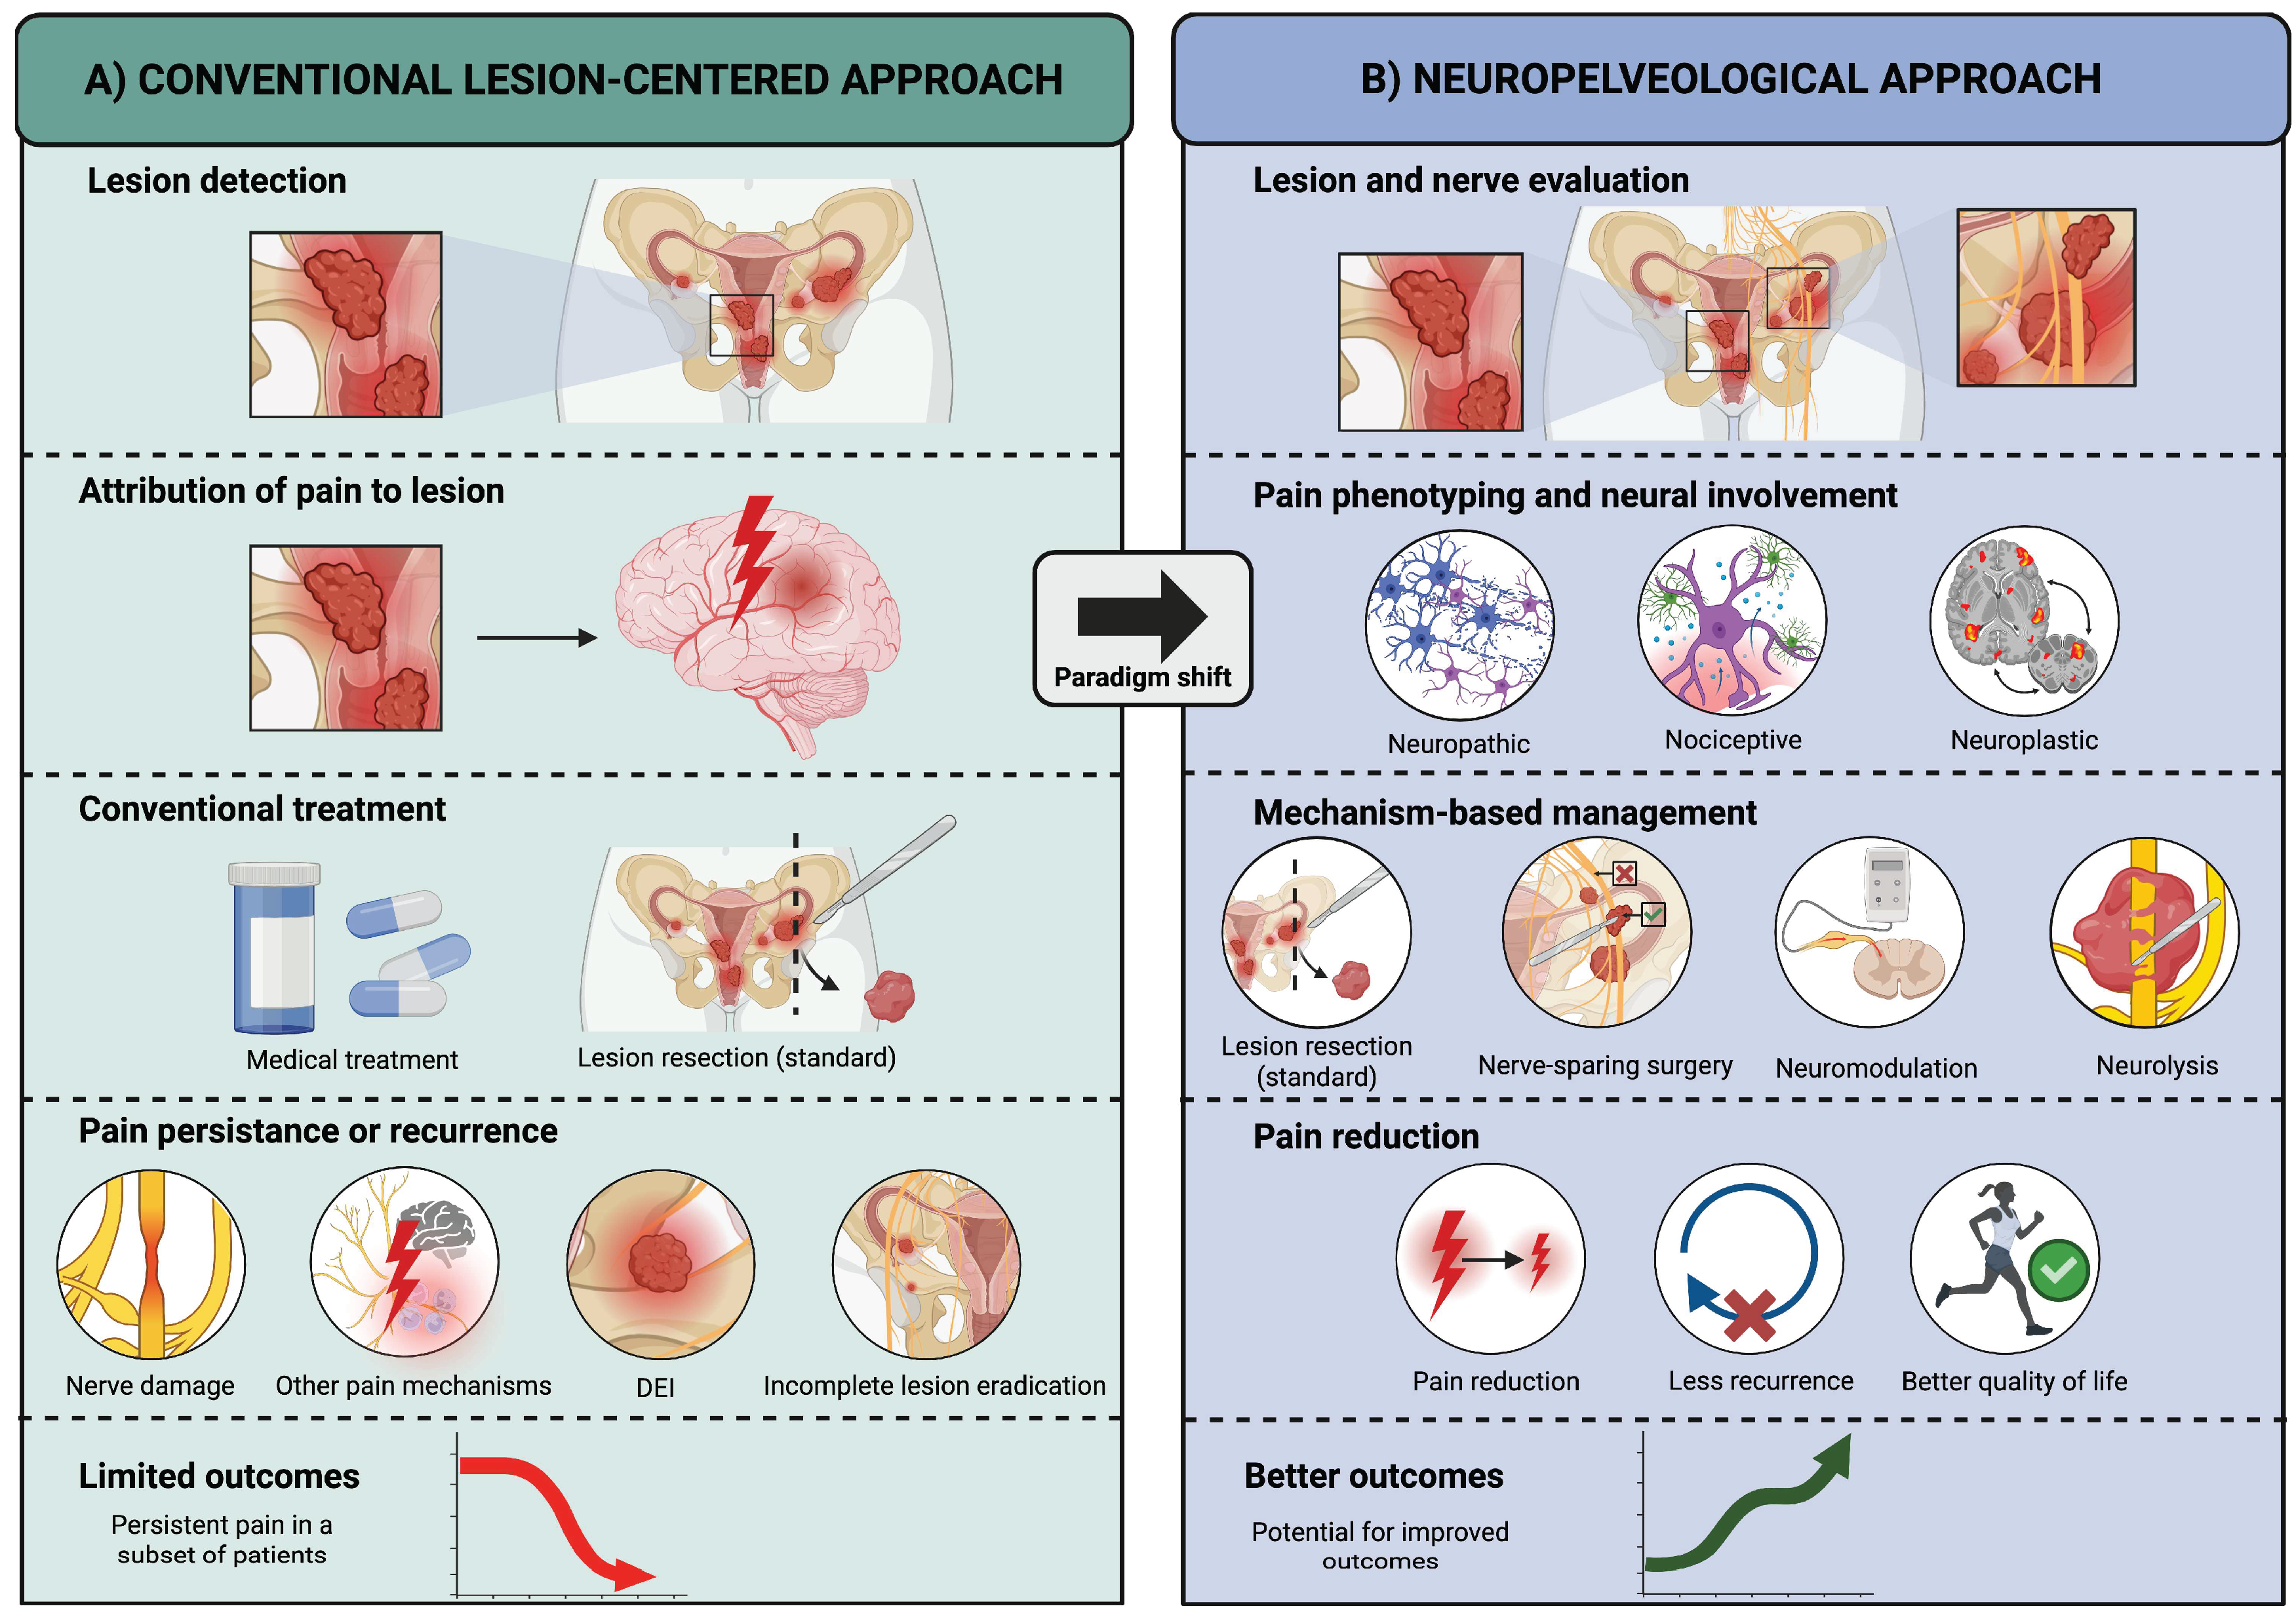

Table 1.
Endometriosis-associated pain phenotypes.
| Pain phenotype | Pathophysiological mechanism | Associated clinical manifestations | Therapeutic approaches | References |
|---|---|---|---|---|
| Nociceptive pain |
|
Dysmenorrhoea, dyspareunia, dyschezia, dysuria, and CPP. |
|
[18,21,25,55]. |
| Neuropathic pain | Lesion or disease affecting the SNS. | Neuropathic symptoms such as radiating pain, paraesthesia, sensory disturbances, and, less frequently, motor deficits. |
Neuromodulators:
|
[18,21,25,55]. |
| Nociplastic pain |
|
Pain hypersensitivity, persistent pain, expansion of the painful area, symptoms disproportionate to the visible tissue damage, CPP. |
|
[22,25]. |
* Table 1. We described the main endometriosis-associated pain phenotypes: nociceptive, neuropathic, and nociplastic pain. Including their underlying pathophysiological mechanism and associated clinical manifestations.
Table 2.
Pelvic innervation components and their associated clinical manifestations. .
| Type of innervation | Involved structures | Neuroanatomical territory | Clinical manifestation | References |
|---|---|---|---|---|
| Somatic |
|
|
|
[38,39]. |
| Autonomic |
|
|
|
[40,41,42,56]. |
| Visceral | Pelvic visceral afferent and efferent fibers. | Pelvic organs involved in urinary, anorectal, and sexual function. |
|
[37,41]. |
* Table 2. The table outlines the main pelvic innervation components, the involved structures, their corresponding neuroanatomical territories and related clinical manifestations. It highlights the importance of pelvic neuroanatomy for the understanding of neuropelveological mechanisms in endometriosis-related pain.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.