
Submitted:
20 August 2026
Posted:
24 August 2026
You are already at the latest version
Abstract
Orofacial myofunctional therapy (OMT) addresses functional impairments involving tongue and lip function, swallowing, and breathing behaviors. Mobile health (mHealth) platforms may facilitate structured delivery and monitoring of home-based exercises, but evidence regarding feasibility in clinical practice remains limited. This study evaluated the feasibility of a smartphone-based OMT platform by examining pre- to post-intervention changes in functional measures and adherence. A retrospective observational analysis was conducted using 15 de-identified clinical records from a single clinical database. Eligible records included documented platform use, baseline and post-intervention measurements, symptoms of at least six months’ duration, and participation in the 16-week intervention. Measures included lip pressure, tongue pressure, swallowing performance, peak nasal inspiratory flow (PNIF), forward head posture, and incentive spirometry. Paired t-tests or Wilcoxon signed-rank tests were used as appropriate. Significant pre- to post-intervention changes were observed in forward head posture, PNIF, incentive spirometry, lip pressure, tongue pressure, and swallowing performance. Adherence was high, with 14 of 15 participants (93%) completing the 16-week program. No adverse events were reported. This retrospective analysis provides preliminary feasibility data for smartphone-delivered OMT. Findings are exploratory and do not establish efficacy, causality, diagnostic validity, or effectiveness for specific medical conditions. Prospective controlled studies using standardized outcome measures are warranted.
Keywords:
orofacial myofunctional therapy
; mobile health
; mHealth
; adherence
; orofacial function
; peak nasal inspiratory flow
1. Introduction
Orofacial myofunctional disorders (OMDs) are characterized by functional disturbances involving the facial, lingual, and oropharyngeal musculature and may be associated with altered swallowing, breathing patterns, speech, and craniofacial posture [1,2]. Previous literature has described OMT in relation to tongue-thrust behaviors, dental occlusion, oral motor function, and other functional concerns [3,4,5,6,7]. These functional concerns occur across pediatric and adult populations, although prevalence estimates vary because of differences in definitions, populations, and assessment methods [8,9].
Orofacial myofunctional therapy has been used for more than a century and incorporates structured exercises intended to improve oral motor function, coordination, and functional patterns [10]. Systematic and quantitative reviews have also identified continued interest in OMT while noting variability in study design, treatment approaches, and outcome measures [11,12].
Adherence is an important consideration in OMT because many therapeutic exercises require repeated practice outside the clinical setting. Previous research has examined strategies for improving adherence to myofunctional therapy, including technology-supported approaches [13,14]. Traditionally conducted through in-person sessions, orofacial myofunctional assessment and therapy have increasingly incorporated web-based and telehealth approaches that may improve accessibility and support remote delivery of care [15,16,17,18]. Telerehabilitation has also been examined specifically for orofacial myofunctional assessment, with evidence of strong agreement between tele-assessment and face-to-face assessment in a sample of individuals with acquired brain injury [18]. Mobile health (mHealth) platforms may provide structured exercise instructions, reminders, performance tracking, and opportunities for clinician oversight that support repeated home practice [19,20,21].
The MyMouthWorks® (MMW) platform (Innovative Therapy 4 Kids, Carlsbad, CA) was developed in 2019 and launched in 2021 [22]. The platform provides structured OMT exercises through a smartphone interface with video demonstrations, audio prompts, exercise tracking, and provider oversight. Exercise modules are assigned according to clinician-entered functional findings.
The purpose of the present study was to conduct a retrospective feasibility analysis of the MMW platform in a real-world clinical setting. The analysis focused on adherence and changes in selected functional measures documented before and after participation in the 16-week program. The study was not designed to validate the platform, establish therapeutic efficacy, determine diagnostic validity, or evaluate treatment of obstructive sleep apnea or other specific medical conditions.
2. Materials and Methods
WCG IRB’s IRB Affairs Department reviewed the study under the Common Rule and applicable guidance and determined that the study was exempt with a waiver of consent under 45 CFR § 46.104(d)(4). Consent for treatment was obtained and was on file with the providers.
Participants and Eligibility
This retrospective observational feasibility study used de-identified clinical records from a single clinical database. Records were screened for participants who had documented use of the MyMouthWorks® (MMW) platform, available baseline and post-intervention measurements, a documented symptom duration of at least six months, and completion or partial completion of the 16-week intervention. Eligible records were included when sufficient clinical documentation was available to characterize the participant’s functional concerns and evaluate pre- and post-intervention outcomes.
Records were excluded if baseline or post-intervention outcome data were unavailable, if no documented functional assessment was available, or if the participant lacked access to a smartphone required for delivery of the intervention.
Because this was a retrospective analysis of existing clinical records, additional clinical variables that could potentially influence or confound orofacial, respiratory, nasal, or sleep-related outcomes were reviewed when documented in the available records. These variables included body mass index (BMI), medication use that could affect sleep or respiratory status, previous OMD treatment, documented ankyloglossia, nasal obstruction, and findings from otolaryngologic (ENT) evaluation. These variables were not required for inclusion because they were not consistently available in the retrospective records and therefore were not used as exclusion criteria or incorporated as covariates in the statistical analysis.
No standardized ENT examination was performed specifically for the purposes of this retrospective study. Participants were therefore characterized according to the functional impairments and clinical findings documented in their existing records rather than according to newly established diagnostic categories. The final sample consisted of participants ranging from 8 to 42 years of age who presented with overlapping functional concerns, including tongue thrust, mouth breathing, and related orofacial and airway-related symptoms.
Sample Size Considerations
Because this was a retrospective feasibility analysis of an existing clinical database, no prospective sample-size calculation was performed. The sample consisted of records that met the predefined eligibility criteria and had available baseline and post-intervention measurements. The sample size was therefore determined by the availability of eligible clinical records rather than by an a priori hypothesis-testing power calculation.
Statistical findings were consequently interpreted as exploratory and hypothesis-generating rather than as evidence of treatment efficacy.
Intervention
The intervention evaluated in this analysis consisted of a 16-week course of structured OMT delivered through the MMW mobile health platform. MMW was the sole intervention evaluated during the 16-week study period, with no concurrent in-person OMT documented in the study records. The platform provided more than 240 guided exercises, including 93 live video demonstrations and 150 narrated text-based exercises. Before each exercise, an animated demonstration or recorded video provided instructions for performing the prescribed activity. Exercise modules were assigned according to clinician-entered functional findings, allowing individualized exercise selections rather than requiring all participants to complete the same exercise sequence.
Exercise sessions required approximately 20 minutes to complete. Prior to each week of prescribed exercises, patients received feedback regarding their performance, expressed as a percentage. Upon completion of exercises, performance data were stored in the platform’s cloud-based system and were available for provider review. Users could also view their daily activity and progress over time. Adherence was recorded through the platform and used to determine completion of the prescribed intervention period.
Examples of exercises included tongue-suction and button-pull exercises. For tongue suction, participants were instructed to keep the lips relaxed, slightly open the mouth, and suction the tongue to the palate for 10 seconds, repeated five times. For button pulls, participants were instructed to sit upright, position a button behind the lips, maintain lip contraction, and pull firmly against the button for 10 seconds while keeping the button in position. These examples represent the types of structured oral motor exercises available through the platform. Additional information regarding the MMW platform is available from the developer’s website [22].
No adverse events or harm were reported in the clinical records reviewed for this analysis.
Outcome Measurement Procedures
Quantitative measurements were obtained using clinical instruments routinely used by the providers and according to manufacturer recommendations.
Forward Head Posture
Forward head posture was assessed using a plumb-line reference to document anterior displacement of the head relative to the postural alignment reference. Measurements were recorded in inches and compared between baseline and post-intervention assessments. The measure was used to describe change in postural alignment within the clinical assessment framework.
Peak Nasal Inspiratory Flow
Peak nasal inspiratory flow (PNIF) was measured using a PNIF meter (GM Instruments Ltd., Ayrshire, UK) and recorded in L/min. PNIF was treated as a measure of nasal inspiratory airflow performance and was not interpreted as a diagnostic measure of sleep-disordered breathing or obstructive sleep apnea.
Incentive Spirometry
Respiratory performance was assessed using incentive spirometry with either a pediatric AirLife Incentive Spirometer (Alabama Healthcare, Muscle Shoals, AL) or an adult Voldyne Incentive Spirometer (Teleflex Medical, Morrisville, NC), according to participant age and clinical use.
Incentive spirometry was included as a functional respiratory performance measure rather than as a direct measure of airway resistance, airway patency, pulmonary function, or lung capacity. Because incentive spirometry primarily assesses inspiratory effort within the testing context, changes in these values were not interpreted as direct evidence of improved airway physiology or pulmonary function.
Lip and Tongue Measurements
Lip and tongue measurements were obtained using the Iowa Oral Performance Instrument (IOPI Medical, Woodinville, WA). Measurements were recorded in kilopascals (kPa) following the prescribed oral motor exercises. The measurements were used to quantify the recorded lip and tongue pressure values within the clinical assessment protocol.
Data Analysis
Nominal variables were summarized using frequency distributions. Quantitative analyses compared baseline and post-intervention measurements. Paired t-tests were used for normally distributed continuous variables, and Wilcoxon signed-rank tests were used for variables that did not meet the assumptions of the paired t-test. Statistical significance was set at p < .05.
Given the retrospective design and small sample size, statistical findings were interpreted as exploratory rather than as evidence of treatment efficacy.
Adherence was calculated from documented completion of the prescribed exercise program. Data were imported into SPSS statistical software (IBM SPSS Statistics for Windows, Version 28.0, Armonk, NY). Prior to analysis, the data were reviewed for potential outliers. The study followed the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines for reporting observational studies.
3. Results
Fifteen participants were included in the analysis. Of these, 73% were female. Participant age ranged from 8 to 42 years (M = 23.33 years, SD = 12.8; median = 20 years). The sample consisted of individuals with overlapping functional concerns related to orofacial and respiratory function (Table 1). Documented functional concerns included tongue-thrust swallowing, mouth breathing, malocclusion, temporomandibular joint-related symptoms, bruxism, headaches/migraines, oral dysphagia, and other clinical findings documented in the records (Figure 1). Because these concerns were overlapping and interdependent, they were not treated as mutually exclusive di agnostic categories or analyzed as separate treatment indications.
3.1. Pre- and Post-Intervention Outcomes
3.1.1. Pre- and post-intervention comparisons demonstrated statistically significant changes across the measured functional variables. Forward head posture decreased significantly following the 16-week intervention period (p < .001), while peak nasal inspiratory flow (PNIF) increased significantly (p = .013) and incentive spirometry increased significantly (p < .001). Recorded orofacial measures also demonstrated significant pre- to post-intervention changes, including lip pressure (p < .001), tongue pressure (p = .012), and swallowing performance (p < .001). Forward head posture decreased by 61.75%, PNIF increased by 79.56%, incentive spirometry increased by 49.62%, lip pressure increased by 31.20%, and tongue pressure increased by 38.86%. Swallowing performance increased from a baseline mean of 2.31% to a post-intervention mean of 81.54%, representing a mean increase of 79.23 percentage points. Because the baseline swallowing value was close to zero, percentage change was not used to characterize the magnitude of this change. Wilcoxon signed-rank analyses confirmed significant pre- to post-intervention changes in lip pressure (Z = −2.83, p = .005), tongue pressure (Z = −2.26, p = .024), and swallowing performance (Z = −3.20, p = .001). Full statistical comparisons are presented in Table 2, Table 3 and Table 4. These findings describe pre- to post-intervention changes within the retrospective sample and do not establish that the intervention caused the observed changes.
3.2. Adherence
Adherence to the intervention was high, with 14 of 15 participants (93%) completing the prescribed 16-week program. One participant did not complete the full 16-week program; however, sufficient baseline and post-intervention data were available for inclusion in the outcome analysis. The observed completion rate supports the feasibility of delivering the prescribed digital intervention within this clinical sample.
4. Discussion
This retrospective observational analysis examined the feasibility of delivering OMT through the MMW mobile health platform in a real-world clinical setting. The study was designed to characterize adherence and changes in selected functional measures documented before and after participation in the 16-week program. It was not designed to validate the platform, establish therapeutic efficacy, determine diagnostic validity, or evaluate treatment of obstructive sleep apnea or another specific medical condition. These distinctions are important when interpreting the observed findings.
The high completion of the prescribed program supports the feasibility of using a structured mobile platform to deliver home-based OMT within this clinical sample. The combination of guided exercises, automated tracking, and provider oversight may provide a practical mechanism for supporting repeated exercise outside the clinical setting. Previous research has examined technology-supported approaches to myofunctional therapy and adherence, including mHealth applications designed to support home-based myofunctional exercise [13,20,21]. However, feasibility should not be equated with effectiveness. Completion of a digital intervention demonstrates that participants were able to engage with the program but does not establish that the intervention produced the functional changes observed.
Changes were observed across several domains of orofacial, nasal, postural, and respiratory performance. The pattern of findings suggests that a digital OMT platform can be used to collect and monitor multiple functional measures within routine clinical care. Systematic reviews of OMT have identified considerable variability in treatment approaches, outcome measures, and study designs, supporting the need for systematic monitoring of multiple functional outcomes when evaluating OMT interventions [11,12]. The observed increase in PNIF is of particular interest because it provides a measure of nasal inspiratory airflow performance. However, PNIF is not a diagnostic measure of obstructive sleep apnea or sleep-disordered breathing. Likewise, incentive spirometry provides information about inspiratory performance within the testing context and should not be interpreted as a direct measure of airway resistance, airway patency, or pulmonary function. The orofacial measurements provide information regarding recorded lip and tongue pressure and swallowing performance but do not, by themselves, establish resolution of a specific disorder.
The observed changes in tongue and orofacial measures should also be interpreted within the context of sensorimotor learning. Proprioceptive assessment is multidimensional, and different assessment methods may capture different aspects of proprioceptive function rather than a single underlying construct [23]. In addition, evidence from proprioception training indicates that learning may demonstrate specificity to the trained task, with acquisition, retention, and transfer varying across training conditions and outcome measures [24]. Accordingly, changes in tongue pressure, swallowing performance, or other functional measures following repeated OMT practice should not automatically be interpreted as evidence of generalized sensorimotor improvement. The present findings therefore provide evidence of change in the recorded clinical measures, but they do not establish broader sensorimotor adaptation or transfer beyond the specific tasks assessed.
Previous studies have examined technology-supported OMT using selected outcomes, including sleep-related measures and tongue function [20,25,26]. The present analysis examined several functional domains within the same clinical dataset, providing a broader description of the types of measurements that may be collected during digitally supported OMT. Sensorimotor tongue evaluation and rehabilitation have previously been investigated in patients with sleep-disordered breathing, demonstrating the potential value of examining tongue function using objective functional measures [26]. Nevertheless, differences in populations, interventions, measurement procedures, and outcome definitions limit direct comparison with previous studies. In particular, the present study did not use a validated sleep outcome instrument or evaluate apnea-hypopnea index and therefore cannot determine whether the observed functional changes correspond to changes in sleep-disordered breathing or obstructive sleep apnea.
The nasal findings also warrant cautious interpretation. Nasal measurements have been investigated in patients with OSA, with recent literature supporting the concept that nasal function may contribute to clinically meaningful phenotypic variation among individuals with OSA [27]. Nasal resistance has also been associated with outcomes of oral appliance treatment in patients with OSA [28]. These findings provide clinical context for including a measure of nasal inspiratory performance in the present analysis; however, they do not establish that an increase in PNIF represents improvement in OSA or sleep-disordered breathing. The present study did not include standardized nasal resistance testing, polysomnography, or another condition-specific assessment capable of determining whether changes in nasal function translated into changes in sleep-related breathing.
The findings may have practical implications for the delivery of home-based OMT. A platform that combines structured exercise instruction with tracking and provider oversight may help integrate repeated home practice into clinical care. Program evaluation in orofacial myology has emphasized the importance of monitoring patient improvement and systematically evaluating clinical outcomes [25]. The feasibility demonstrated in this sample provides a basis for further investigation of whether specific patterns of adherence are associated with meaningful functional improvement. Future research should also examine whether digital delivery produces outcomes comparable to conventional in-person therapy.
Several limitations must be considered. The retrospective design, small sample size, and absence of a control group prevent causal inference and limit generalizability. Changes observed between baseline and post-intervention assessment may reflect factors other than the intervention, including repeated measurement, natural variation, concurrent clinical care, or regression to the mean. In addition, potentially important clinical variables, including BMI, medication use that could affect sleep or respiratory status, previous OMD treatment, ankyloglossia, nasal obstruction, and ENT findings, were not consistently available and therefore could not be incorporated into the analysis. No standardized ENT examination was performed for the purposes of this study. Some measurements were obtained through routine clinical documentation rather than a prospective standardized research protocol, and patient-reported sleep observations were not collected using a validated sleep questionnaire. These limitations further restrict interpretation of the observed changes and reinforce the need for prospective studies using standardized assessment procedures and condition-specific outcomes.
These findings support the feasibility of studying digitally delivered OMT in clinical practice, rather than demonstrating treatment efficacy. The results are preliminary and hypothesis-generating. Prospective controlled studies with larger and more diverse samples, standardized measurement procedures, validated condition-specific outcomes, clearly defined exercise protocols, systematic assessment of potential confounders, and longer follow-up are needed to determine the clinical significance, reproducibility, and durability of the observed changes. Future studies should also examine whether adherence to digitally delivered OMT is associated with changes in specific functional outcomes and whether those changes are retained or transferred beyond the trained tasks.
5. Conclusions
A structured mobile health platform was feasible for delivering and monitoring a 16-week course of orofacial myofunctional therapy in this retrospective clinical sample. High program completion and observed pre- to post-intervention changes across selected functional measures provide preliminary feasibility data for digitally supported OMT. These findings do not establish treatment efficacy, causality, diagnostic validity, or effectiveness for specific medical conditions. Prospective controlled studies using standardized outcome measures are warranted.
Author Contributions
Both authors reviewed and approved the final manuscript. Conceptualization, K.P.D.; methodology, K.P.D.; validation, K.P.D. and T.M.; formal analysis, K.P.D.; investigation, K.P.D.; data curation, T.M.; writing—original draft preparation, K.P.D.; writing—review and editing, K.P.D. and T.M.
Funding
This research received no external funding.
Institutional Review Board Statement
WCG IRB’s IRB Affairs Department reviewed the study under the Common Rule and applicable guidance and determined that the study was exempt with a waiver of consent under 45 CFR § 46.104(d)(4).
Informed Consent Statement
Consent for treatment was obtained and was on file with the providers.
Data Availability Statement
The data presented in this study are available on reasonable request from the corresponding author. The data are not publicly available because they are derived from de-identified clinical records and may contain information subject to privacy and confidentiality restrictions.
Conflicts of Interest
Tom Milroy is an employee of Innovative Oral Solutions, Inc. and Innovative Therapy 4 Kids, Inc. Karen Parker Davidson declares no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| BMI | Body Mass Index |
| ENT | Ear, Nose, and Throat (Otolaryngologic) |
| IRB | Institutional Review Board |
| mHealth | Mobile Health |
| MMW | MyMouthWorks® |
| OMD | Orofacial Myofunctional Disorder |
| OMT | Orofacial Myofunctional Therapy |
| PNIF | Peak Nasal Inspiratory Flow |
| STROBE | Strengthening the Reporting of Observational Studies in Epidemiology |
References
- Alhazmi, W. A. Mouth Breathing and Speech Disorders: A Multidisciplinary Evaluation Based on The Etiology. J. Pharm. Bioallied Sci. 2022, 14 (Suppl 1), S911–S916. [Google Scholar] [CrossRef]
- Hanson, M. L. Orofacial myofunctional therapy: historical and philosophical considerations. The International journal of orofacial myology: official publication of the International Association of Orofacial Myology 1988, 14(1), 3–10. [Google Scholar] [CrossRef]
- Shah, S. S.; Nankar, M. Y.; Bendgude, V. D.; Shetty, B. R. Orofacial Myofunctional Therapy in Tongue Thrust Habit: A Narrative Review. Int. J. Clin. Pediatr. Dent. 2021, 14(2), 298–303. [Google Scholar] [CrossRef]
- Benkert, K. K. The effectiveness of orofacial myofunctional therapy in improving dental occlusion. The International journal of orofacial myology: official publication of the International Association of Orofacial Myology 1997, 23, 35–46. [Google Scholar] [CrossRef]
- Meyer, P. G. Tongue lip and jaw differentiation and its relationship to orofacial myofunctional treatment. The International journal of orofacial myology: official publication of the International Association of Orofacial Myology 2000, 26, 44–52. [Google Scholar] [CrossRef]
- Kellum, G. D.; Gross, A. M.; Hale, S. T.; Eiland, S.; Williams, C. Thumbsucking as related to placement and acoustic aspects of /s, z/ and lingual rest postures. Int. J. Orofac. Myol. 1994, 20(1), 4–9. [Google Scholar] [CrossRef]
- Rogers, A. P. Exercises for the development of muscles of face with view to increasing their functional activity. Dent. Cosm. LX 1918, 59(857), e76. [Google Scholar]
- Wadsworth, S. D.; Maul, C. A.; Stevens, E. J. The prevalence of orofacial myofunctional disorders among children identified with speech and language disorders in grades kindergarten through six. The International journal of orofacial myology: official publication of the International Association of Orofacial Myology 1998, 24, 1–19. [Google Scholar] [CrossRef]
- Coça, K. L.; Bergmann, A.; Ferman, S.; Angelis, E. C.; Ribeiro, M. G. Prevalence of communication, swallowing and orofacial myofunctional disorders in children and adolescents at the time of admission at a cancer hospital. Prevalência de distúrbios da comunicação, deglutição e motricidade orofacial em crianças e adolescentes no momento da matrícula em um hospital oncológico. CoDAS 2018, 30(1), e20170123. [Google Scholar] [CrossRef]
- Wishney, M.; Darendeliler, M.A.; Dalci, O. Myofunctional therapy and prefabricated functional appliances: an overview of the history and evidence. Aust. Dent. J. 2018, 64, 135–144. [Google Scholar] [CrossRef]
- Stefani, C. M.; de Almeida de Lima, A.; Stefani, F. M.; Kung, J. Y.; Flores-Mir, C.; Compton, S. M. Effectiveness of orofacial myofunctional therapy in improving orofacial function and oral habits: a scoping review. Can. J. Dent. Hyg. CJDH J. Can. De L’hygiene Dent. JCHD 2025, 59(1), 59–72. [Google Scholar]
- Shortland, H. L.; Hewat, S.; Vertigan, A.; Webb, G. Orofacial Myofunctional Therapy and Myofunctional Devices Used in Speech Pathology Treatment: A Systematic Quantitative Review of the Literature. Am. J. Speech-Lang. Pathol. (Online) 2021, 30(1), 301–317. [Google Scholar] [CrossRef]
- O’Connor-Reina, C.; Ignacio Garcia, J.M.; Rodriguez Alcala, L.; Rodríguez Ruiz, E.; Garcia Iriarte, M.T.; Casado Morente, J.C.; Baptista, P.; Plaza, G. Improving Adherence to Myofunctional Therapy in the Treatment of Sleep-Disordered Breathing. J. Clin. Med. 10 2021, 5772. [Google Scholar] [CrossRef]
- Diaféria, G.; Santos-Silva, R.; Truksinas, E.; Haddad, F. L.; Santos, R.; Bommarito, S., ...; Bittencourt, L. Myofunctional therapy improves adherence to continuous positive airway pressure treatment. Sleep Breath. 2017, 21, 387–395. [Google Scholar] [CrossRef]
- Wantland, D. J.; Portillo, C. J.; Holzemer, W. L.; Slaughter, R.; McGhee, E. M. The effectiveness of web-based vs. non-web-based interventions: a meta-analysis of behavioral change outcomes. J. Med. Internet Res. 2004, 6(4), e40. [Google Scholar] [CrossRef]
- Eysenbach, G.; CONSORT-EHEALTH Group. CONSORT-EHEALTH: improving and standardizing evaluation reports of web-based and mobile health interventions. J. Med. Internet Res. 2011, 13(4), e126. [Google Scholar] [CrossRef] [PubMed]
- Hyder, M. A.; Razzak, J. Telemedicine in the United States: An Introduction for Students and Residents. J. Med. Internet Res. 2020, 22(11), e20839. [Google Scholar] [CrossRef]
- Zapata-Soria, M.; Muñoz-Vigueras, N.; Cabrera-Martos, I.; López-López, L.; Ortiz-Rubio, A.; Valenza, M. C. Agreement between telerehabilitation and face-to-face orofacial myofunctional assessment in persons with acquired brain injury. Brain Inj. 2023, 37(8), 669–674. [Google Scholar] [CrossRef]
- Isetta, V.; Torres, M.; González, K.; Ruiz, C.; Dalmases, M.; Embid, C.; Navajas, D.; Farré, R.; Montserrat, J. M. A New mHealth application to support treatment of sleep apnoea patients. J. Telemed. Telecare 2017, 23(1), 14–18. [Google Scholar] [CrossRef]
- O’Connor Reina, C.; Plaza, G.; Ignacio-Garcia, J.M.; et al. New mHealth application software based on myofunctional therapy applied to sleep-disordered breathing in non-compliant subjects. Sleep Sci. Pract. 2020, 4(3). [Google Scholar] [CrossRef]
- Anderson, K.; Burford, O.; Emmerton, L. Mobile Health Apps to Facilitate Self-Care: A Qualitative Study of User Experiences. PLoS ONE 2016, 11(5), e0156164. [Google Scholar] [CrossRef]
- MyMouthworks. About Us . n.d. Available online: https://iosmmw.com/about-my-mouth/.
- Horváth, Á.; Ferentzi, E.; Schwartz, K.; Jacobs, N.; Meyns, P.; Köteles, F. The measurement of proprioceptive accuracy: A systematic literature review. J. Sport Health Sci. 2023, 12(2), 219–225. [Google Scholar] [CrossRef]
- Seo, H. G.; Yun, S. J.; Farrens, A. J.; Johnson, C. A.; Reinkensmeyer, D. J. A Systematic Review of the Learning Dynamics of Proprioception Training: Specificity, Acquisition, Retention, and Transfer. Neurorehabilit. Neural Repair. 2023, 37(10), 744–757. [Google Scholar] [CrossRef]
- Keatley, M. A.; Coulson, S. Program evaluation in orofacial myology: implications for monitoring patient improvement, profitability of service and marketing your practice. Int. J. Orofac. Myol. 1989, 15(3), 8–15. [Google Scholar] [CrossRef]
- Rodríguez-Alcalá, L.; Martínez, J. M.; Baptista, P.; Ríos Fernández, R.; Javier Gómez, F.; Parejo Santaella, J.; Plaza, G. Sensorimotor tongue evaluation and rehabilitation in patients with sleep-disordered breathing: a novel approach. J. Oral Rehabil. 2021, 48(12), 1363–1372. [Google Scholar] [CrossRef]
- Hoel, H. C.; Kvinnesland, K.; Berg, S. Outcome of nasal measurements in patients with OSA - Mounting evidence of a nasal endotype. Sleep Med. 2023, 103, 131–137. [Google Scholar] [CrossRef]
- Zeng, B.; Ng, A. T.; Qian, J.; Petocz, P.; Darendeliler, M. A.; Cistulli, P. A. Influence of nasal resistance on oral appliance treatment outcome in obstructive sleep apnea. Sleep 2008, 31(4), 543–547. [Google Scholar] [CrossRef]
Figure 1.
Frequency Distribution of Documented Functional Concerns in the Sample.
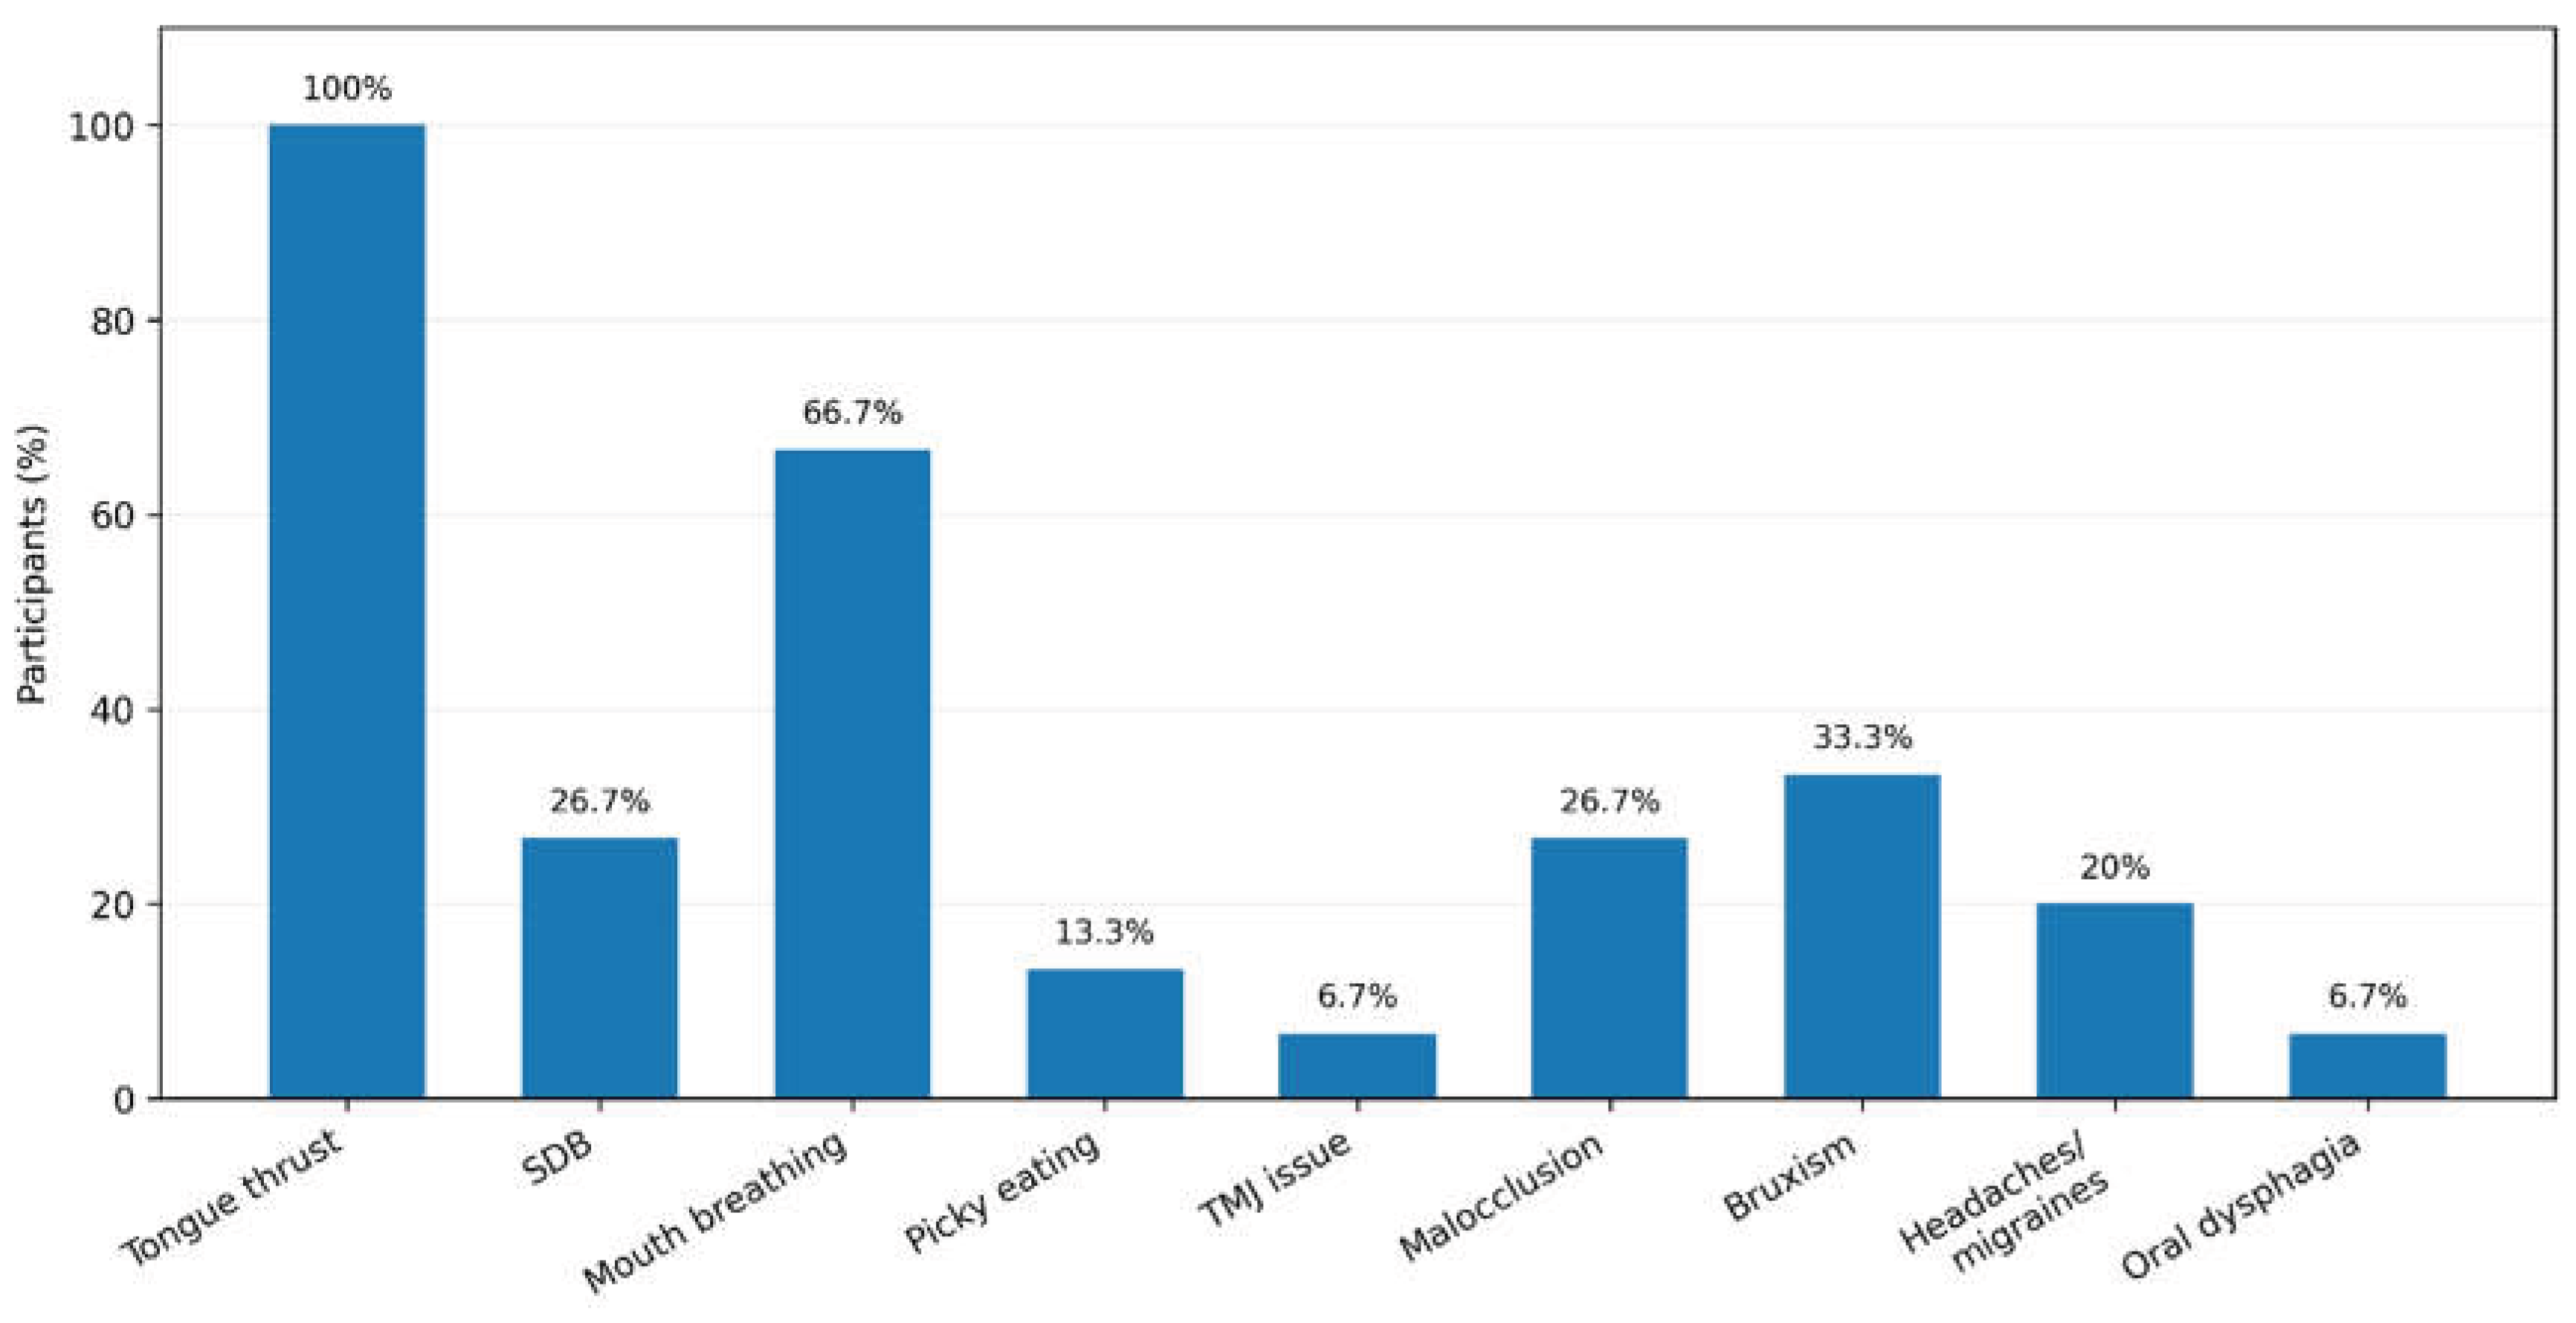

Table 1.
Frequency Distribution of the Sample (N=15).
| N | Percentage | Min | Max | Mean | Median | |
| Gender | 15 | |||||
| Females | 11 | 73% | ||||
| Males | 4 | 27% | ||||
| Age in Years (Mean) | 23.33 | 8 | 42 | 20 | ||
| # of Functional Concerns for the Program | 1 | 4 | 3 | |||
| Four | 5 | 33% | ||||
| Three | 6 | 40% | ||||
| Two | 3 | 20% | ||||
| One | 1 | 6% |
Table 2.
Pre and post measurements show statistically significant improvement after using the platform for 16 weeks.
Table 2.
Pre and post measurements show statistically significant improvement after using the platform for 16 weeks.
| Mean | Std. Dev. | Std. Error Mean | 95% Confidence Interval of the Difference | t | df | One- Sided p |
Two-Sided p | ||
| Lower | Upper | ||||||||
| Forward Head Posture Pre - Forward Head Posture Post | 1.31 | .830 | .23023 | .806 | 1.81 | 5.68 | 12 | <.001 | <.001 |
| PNIF Post (L/Min) - PNIF Pre (L/Min) | 63.50 | 40.97 | 16.727 | 20.50 | 106.50 | 3.79 | 5* | .006 | .013 |
| Spirom Post (ml) - Spirom Pre (ml) | 763.46 | 420.27 | 116.56 | 509.50 | 1017.42 | 6.55 | 12 | <.001 | <.001 |
| Lip Pressure Post (kPa) - Lip Pressure Pre (kPa) | 6.65 | 5.12 | 1.42 | 3.55 | 9.75 | 4.68 | 12 | <.001 | <.001 |
| Tongue Pressure Post (kPa) - Tongue Pressure Pre (kPa) | 14.35 | 18.51 | 4.95 | 3.66 | 25.04 | 2.90 | 13 | .006 | .012 |
| Swallow Percent Post - Swallow Percent Pre | 79.23 | 22.15 | 6.15 | 65.84 | 92.62 | 12.89 | 12 | <.001 | <.001 |
*Because PNIF measurements were not available at both time points for all participants, the paired PNIF analysis was based on the subset with complete pre- and post-intervention measurements.
Table 3.
Pre- and post-intervention comparisons of measured functional outcomes.
| Mean | Std. Deviation | Std. Error Mean | Percent of Change | ||
| Forward Head Posture Pre (inches) | 2.11 | 1.00 | .27824 | ||
| Forward Head Posture Post (inches) | .807 | .596 | .16543 | 61.75 decrease | |
| PNIF Nasal Flow Pre (L/Min) | 79.83 | 19.63 | 8.014 | ||
| PNIF Nasal Flow Post (L/Min) | 143.33 | 27.70 | 8.014 | 79.56 increase | |
| Spirometry Pre (ml) | 1538.46 | 624.55 | 173.219 | ||
| Spirometry Post (ml) | 2301.92 | 596.47 | 165.431 | 49.62 increase | |
| Lip Pressure Pre (kPa) | 21.31 | 6.81 | 1.88919 | ||
| Lip Pressure Post (kPa) | 27.96 | 4.43 | 1.22927 | 31.20 increase | |
| Tongue Pressure Pre (kPa) | 36.93 | 21.12 | 5.64467 | ||
| Tongue Pressure Post (kPa) | 51.28 | 11.37 | 3.03899 | 38.86 increase | |
| Swallow Percent Pre | 2.31 | 8.32 | 2.30769 | ||
| Swallow Percent Post | 81.54 | 21.54 | 5.97496 | 79.23 increase | |
Table 4.
Improvements in orofacial function Lip Pressure (kPa) Tongue Pressure (kPa) Swallowing.
| Z | -2.83c | -2.26c | -3.20c |
| Asymp. Sig. (2-tailed) | .005 | .024 | .001 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.