

Submitted:
14 August 2026
Posted:
14 August 2026
You are already at the latest version
Abstract
Background/Objectives: Rotavirus vaccination reduces severe childhood gastroenteritis, but real-world effectiveness may vary across settings and calendar periods. We estimated the effectiveness of documented complete rotavirus vaccination against laboratory-confirmed rotavirus gastroenteritis and rotavirus-associated hospitalization among children younger than 5 years in Türkiye. Methods: This retrospective test-negative study included children aged 0–59 months who underwent stool rotavirus testing for clinically evaluated acute gastroenteritis at a tertiary hospital between January 2015 and June 2026. Tests occurring within 14 days in the same child were combined into one episode. Cases were rotavirus-positive episodes and controls were rotavirus-negative episodes. Complete vaccination was defined by an institutional record showing completion of the full schedule before the index test. Cluster-robust logistic regression adjusted for age group, sex, treatment setting, calendar year, and test month. Vaccine effectiveness (VE) was calculated as (1−adjusted odds ratio)×100%. Results: The analysis included 2,788 episodes among 2,242 children: 534 rotavirus-positive cases and 2,254 test-negative controls. Complete vaccination was documented in 81 cases (15.2%) and 539 controls (23.9%). Crude VE was 43.1% (95% confidence interval [CI], 26.2%–56.1%). Adjusted VE against laboratory-confirmed rotavirus gastroenteritis was 52.8% (95% CI, 37.6%–64.3%; P<0.001). Among hospitalized episodes, adjusted VE was 57.8% (95% CI, 33.5%–73.2%; P<0.001). Estimates were stable when vaccination completion was required at least 14 days before testing, when only the first episode per child was retained, and with 7- or 30-day episode definitions. Effectiveness varied markedly by calendar period: 15.3% (95% CI, −28.7% to 44.3%) in 2015–2019 and 77.7% (95% CI, 62.3%–86.8%) in 2022–2026. Conclusions: Documented complete rotavirus vaccination was associated with substantially lower odds of laboratory-confirmed rotavirus gastroenteritis and rotavirus-associated hospitalization. The marked period-specific variation indicates that the pooled estimate should be interpreted with attention to changes in epidemiology, testing, healthcare utilization, and residual confounding across the COVID-19 era.
Keywords:
rotavirus
; vaccination
; vaccine effectiveness
; test-negative design
; acute gastroenteritis
; hospitalization
; children
1. Introduction
Rotavirus remains an important cause of acute gastroenteritis, dehydration, emergency care, and hospitalization among young children. Although mortality has declined substantially in many settings, rotavirus continues to impose a clinically meaningful burden, particularly among children younger than 5 years. The World Health Organization recommends inclusion of rotavirus vaccination in national immunization programs as part of a comprehensive strategy for prevention and treatment of childhood diarrheal disease [1].
Randomized trials of the monovalent and pentavalent vaccines established high efficacy against severe rotavirus gastroenteritis [2,3,4]. Subsequent observational studies and meta-analyses confirmed large reductions in rotavirus-associated emergency visits, hospitalization, and mortality, while also showing that effectiveness varies across geographic regions, income settings, age groups, and outcome severity [5,6,7]. Recent hospital-based surveillance in the United States reported strong protection against emergency department visits and hospitalization and even higher effectiveness against very severe disease [8].
Türkiye presents a distinct setting for vaccine-effectiveness evaluation because rotavirus vaccination has historically been self-financed rather than universally funded. Consequently, uptake and documentation may differ from countries with national programs. Turkish multicenter surveillance established a substantial burden of rotavirus gastroenteritis [9], while a subsequent observational study reported that self-financed vaccination was associated with fewer rotavirus-positive episodes and severe outcomes [10].
The test-negative design is well suited to post-licensure vaccine-effectiveness research. By comparing vaccination status between patients who seek care for the same clinical syndrome but differ in laboratory result, the design can reduce bias related to healthcare-seeking and access to testing [11,12]. Nevertheless, it remains vulnerable to exposure misclassification, temporal changes in testing, residual confounding, and differential selection into the tested population.
These concerns are especially relevant to long study periods spanning the COVID-19 pandemic. Public-health interventions, changes in childcare attendance, altered healthcare-seeking, diagnostic practices, admission thresholds, and disrupted rotavirus circulation may change both the composition of tested patients and the apparent effectiveness of vaccination. Recent pediatric data from Türkiye and other settings demonstrate substantial pandemic-associated changes in rotavirus activity and clinical presentation [13,14,15].
The primary objective of this study was to estimate the effectiveness of documented complete rotavirus vaccination against laboratory-confirmed rotavirus gastroenteritis among children aged 0–59 months using an 11-year test-negative design. Secondary objectives were to estimate effectiveness against rotavirus-associated hospitalization, assess the robustness of the estimate under alternative episode and exposure definitions, and explore calendar-period variation.
2. Materials and Methods
2.1. Study Design and Setting
This retrospective, single-center test-negative study was conducted at Hisar Hospital Intercontinental, a tertiary-care hospital in Istanbul, Türkiye. The study population comprised children aged 0–59 completed months who underwent stool rotavirus antigen testing during an acute gastroenteritis evaluation between 1 January 2015 and 30 June 2026. The report was prepared in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology recommendations [16].
2.2. Data Sources and Linkage
Laboratory and clinical records provided the institutional protocol number, treatment number, sex, date of birth, test date, rotavirus result, and treatment setting. A separate institutional vaccination database identified children with a documented completed rotavirus vaccination schedule. The databases were linked deterministically using the unique institutional protocol number. Sex was concordant in all linked records.
2.3. Eligibility and Episode Construction
Eligible records were rotavirus tests from children aged 0–59 months with a definitive positive or negative result and complete information on date of birth, test date, sex, and treatment setting. To avoid counting repeat testing during the same illness as independent observations, tests occurring within 14 days of a prior test in the same child were combined into one acute gastroenteritis episode. An episode was classified as positive if any test within the episode was positive; the earliest positive test was the index test for cases, and the first test was the index test for controls. Hospitalization was recorded when any encounter in the episode was inpatient. Alternative 7- and 30-day windows were examined in sensitivity analyses.
2.4. Case and Control Definitions
Cases were eligible acute gastroenteritis episodes with a positive stool rotavirus result. Controls were eligible episodes with a negative rotavirus result. Test-negative controls were drawn from the same institution, age range, study period, testing process, and clinical pathway as cases.
2.5. Vaccination Exposure
Complete vaccination was defined as a documented age-appropriate full course completed on or before the index test date: three doses of the pentavalent vaccine (RotaTeq) or two doses of the monovalent vaccine (Rotarix). Dose dates and vaccine product were verified in the institutional vaccination records. Children classified as unvaccinated had documented confirmation that they had received no rotavirus vaccine; therefore, absence of a complete schedule was not used as a proxy for unvaccinated status. The primary analysis combined the two licensed complete schedules and did not perform product-specific comparisons. A sensitivity analysis required the final dose to have been administered at least 14 days before the index test.
2.6. Outcomes
The primary outcome was laboratory-confirmed rotavirus gastroenteritis. The principal secondary outcome was rotavirus-associated hospitalization, evaluated by restricting the test-negative analysis to hospitalized acute gastroenteritis episodes. A complementary analysis restricted to rotavirus-positive cases evaluated whether complete vaccination was associated with hospitalization conditional on breakthrough infection.
2.7. Statistical Analysis
Continuous variables were summarized as medians and interquartile ranges (IQRs), and categorical variables as frequencies and percentages. Group comparisons used the Mann–Whitney U test for age and the chi-square or Fisher exact test for categorical variables, as appropriate.
Crude odds ratios (ORs) were estimated from 2×2 tables. The primary multivariable logistic model included complete vaccination, age group (0–5, 6–11, 12–23, 24–35, and 36–59 months), sex, inpatient versus noninpatient setting, calendar-year fixed effects, and test-month fixed effects. Cluster-robust standard errors accounted for multiple episodes contributed by the same child. Vaccine effectiveness was calculated as (1−OR)×100%, with confidence limits derived by transforming the OR confidence interval.
Prespecified sensitivity analyses used 7- and 30-day episode windows, restricted the cohort to the first episode per child, required vaccination completion at least 14 days before testing, used a more parsimonious period-adjusted model, and analyzed hospitalized and nonhospitalized episodes separately. Exploratory analyses estimated effectiveness during 2015–2019, 2020–2021, and 2022–2026. Between-period heterogeneity was assessed using an inverse-variance Q statistic. Two-sided P<0.05 was considered statistically significant. Analyses were performed using Python with pandas, NumPy, and SciPy.
2.8. Ethics
The protocol was reviewed as a retrospective analysis of routinely collected clinical data by the institutional ethics committee. The formal committee name, approval number, approval date, and consent-waiver wording must be confirmed against the ethics decision before submission.
3. Results
3.1. Study Population
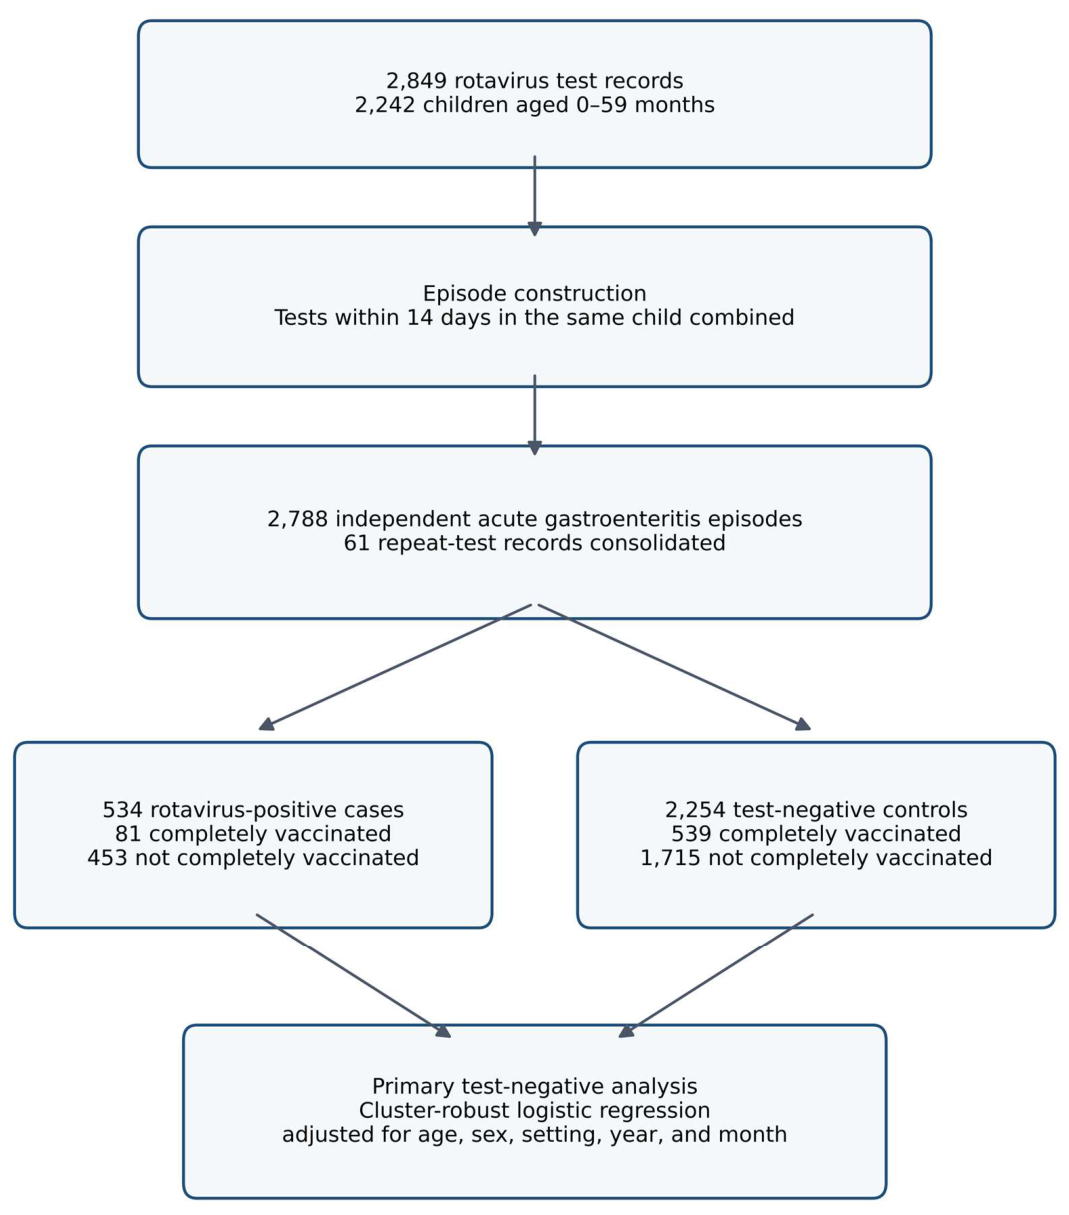
The source file contained 2,849 rotavirus test records from 2,242 children. Consolidating repeat tests within 14 days produced 2,788 independent acute gastroenteritis episodes. Sixty-one repeat-test records were combined, and 10 episode groups contained discordant sequential results. The final cohort included 534 rotavirus-positive cases and 2,254 test-negative controls (Figure 1).
Complete vaccination before testing was documented in 620 episodes (22.2%). Vaccination was documented in 81 of 534 cases (15.2%) and 539 of 2,254 controls (23.9%). The median age was 25.8 months (IQR, 14.9–40.3) among cases and 22.4 months (IQR, 10.8–38.7) among controls. Sex and treatment-setting distributions were similar between cases and controls, whereas age and calendar time differed significantly.

Table 1.
Characteristics of test-negative controls and rotavirus-positive cases.
| Characteristic | N | Age, months, median (IQR) | Male, n (%) | Hospitalized, n (%) | Complete vaccination, n (%) |
|---|---|---|---|---|---|
| Test-negative controls | 2254 | 22.4 (11.0–38.9) | 1233 (54.7) | 1062 (47.1) | 539 (23.9) |
| Rotavirus-positive cases | 534 | 25.8 (14.9–40.2) | 284 (53.2) | 241 (45.1) | 81 (15.2) |
| P value | — | <0.001 | 0.558 | 0.436 | <0.001 |
3.2. Primary Vaccine-Effectiveness Analysis
Rotavirus positivity occurred in 81 of 620 completely vaccinated episodes (13.1%) and 453 of 2,168 episodes without complete vaccination before testing (20.9%). The crude OR was 0.57 (95% CI, 0.44–0.74), corresponding to a crude VE of 43.1% (95% CI, 26.2%–56.1%; P<0.001). After adjustment for age group, sex, treatment setting, calendar year, and test month, the OR was 0.47 (95% CI, 0.36–0.62), corresponding to an adjusted VE of 52.8% (95% CI, 37.6%–64.3%; P<0.001).
3.3. Effectiveness Against Rotavirus-Associated Hospitalization
Among 1,303 hospitalized acute gastroenteritis episodes, 241 were rotavirus positive and 1,062 were test-negative controls. Complete vaccination was associated with an adjusted VE of 57.8% (95% CI, 33.5%–73.2%; P<0.001) against hospitalized rotavirus gastroenteritis. Among 1,485 nonhospitalized episodes, adjusted VE was 52.2% (95% CI, 32.2%–66.3%; P<0.001).
In the complementary case-only analysis restricted to 534 rotavirus-positive episodes, complete vaccination was not independently associated with hospitalization after adjustment (OR, 0.97; 95% CI, 0.51–1.82; P=0.921). This finding indicates that the principal measurable benefit was a lower likelihood of becoming a rotavirus-positive case among tested children, including among hospitalized presentations, rather than reduced hospitalization conditional on breakthrough infection.
Table 2.
Vaccine effectiveness against laboratory-confirmed rotavirus gastroenteritis.
| Analysis | Episodes | Cases | OR (95% CI) | VE %, (95% CI) | P value |
|---|---|---|---|---|---|
| Crude overall | 2788 | 534 | 0.57 (0.44–0.74) | 43.1 (26.2 to 56.1) | <0.001 |
| Adjusted overall | 2788 | 534 | 0.47 (0.36–0.62) | 52.8 (37.6 to 64.3) | <0.001 |
| Hospitalized episodes | 1303 | 241 | 0.42 (0.27–0.66) | 57.8 (33.5 to 73.2) | <0.001 |
| Nonhospitalized episodes | 1485 | 293 | 0.48 (0.34–0.68) | 52.2 (32.2 to 66.3) | <0.001 |
3.4. Sensitivity Analyses
The primary estimate was stable across alternative analytical definitions. Requiring vaccination completion at least 14 days before testing yielded VE of 54.1% (95% CI, 39.3%–65.3%). Restriction to the first episode per child yielded VE of 55.4% (95% CI, 38.3%–67.8%). Estimates using 7- and 30-day episode windows were 52.8% and 52.9%, respectively. The parsimonious period-adjusted model produced VE of 51.2% (95% CI, 35.9%–62.8%).
Table 3.
Sensitivity analyses.
| Analysis | Episodes | Cases | Adjusted VE %, (95% CI) | P value |
|---|---|---|---|---|
| Completion ≥14 days | 2788 | 534 | 54.1 (39.3 to 65.3) | <0.001 |
| First episode per child | 2242 | 445 | 55.4 (38.3 to 67.8) | <0.001 |
| 7-day episode window | 2811 | 534 | 52.8 (37.7 to 64.3) | <0.001 |
| 30-day episode window | 2753 | 534 | 52.9 (37.8 to 64.4) | <0.001 |
| Parsimonious period model | 2788 | 534 | 51.2 (35.9 to 62.8) | <0.001 |
3.5. Calendar-Period Variation
Rotavirus positivity and the number of tests varied substantially by year (Figure 3). Adjusted VE was 15.3% (95% CI, −28.7% to 44.3%; P=0.437) during 2015–2019, 35.9% (95% CI, −105.5% to 80.0%; P=0.454) during 2020–2021, and 77.7% (95% CI, 62.3%–86.8%; P<0.001) during 2022–2026. The pandemic-period estimate was imprecise because only 27 positive episodes occurred. Exploratory between-period heterogeneity was significant (Q=15.36; P<0.001).
Figure 2.
Adjusted vaccine-effectiveness estimates for the primary, setting-specific, and sensitivity analyses. Points indicate vaccine-effectiveness estimates and horizontal lines indicate 95% confidence intervals.
Figure 2.
Adjusted vaccine-effectiveness estimates for the primary, setting-specific, and sensitivity analyses. Points indicate vaccine-effectiveness estimates and horizontal lines indicate 95% confidence intervals.
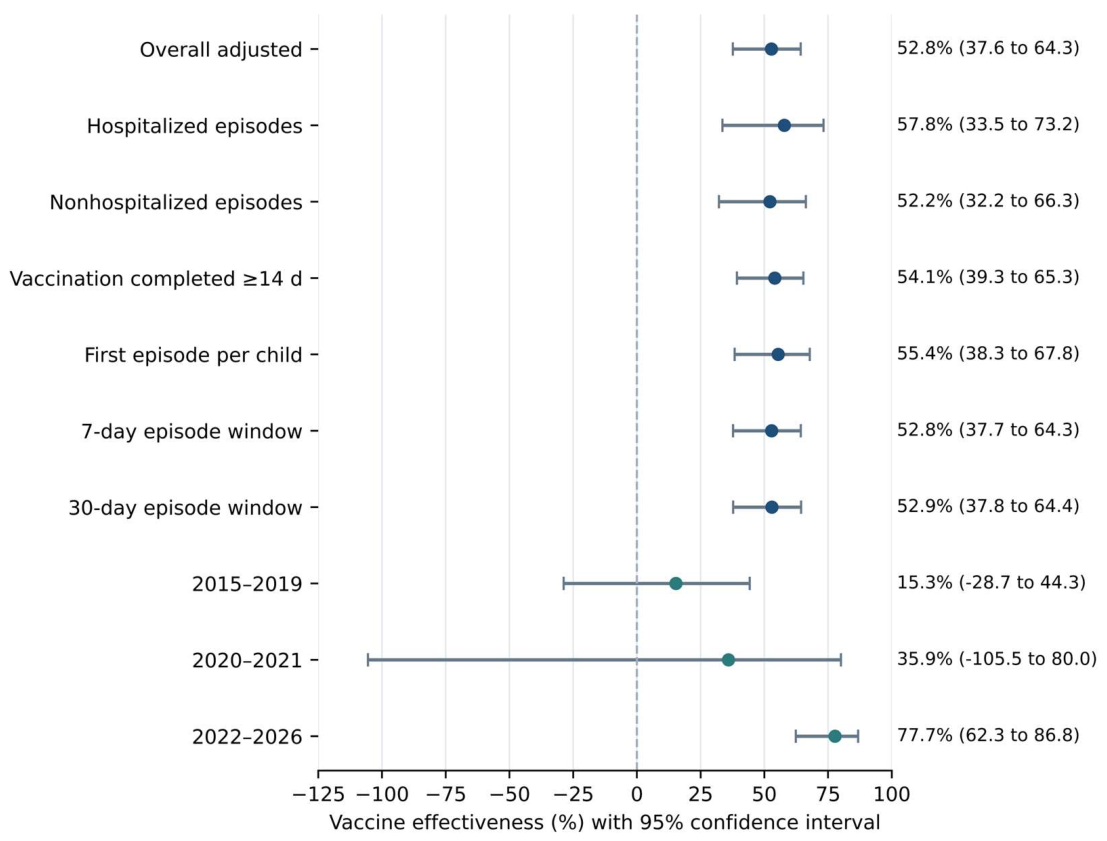
Figure 3.
Annual numbers of acute gastroenteritis episodes tested and the proportion positive for rotavirus during 2015–2026. Data for 2026 include January through June only.
Figure 3.
Annual numbers of acute gastroenteritis episodes tested and the proportion positive for rotavirus during 2015–2026. Data for 2026 include January through June only.
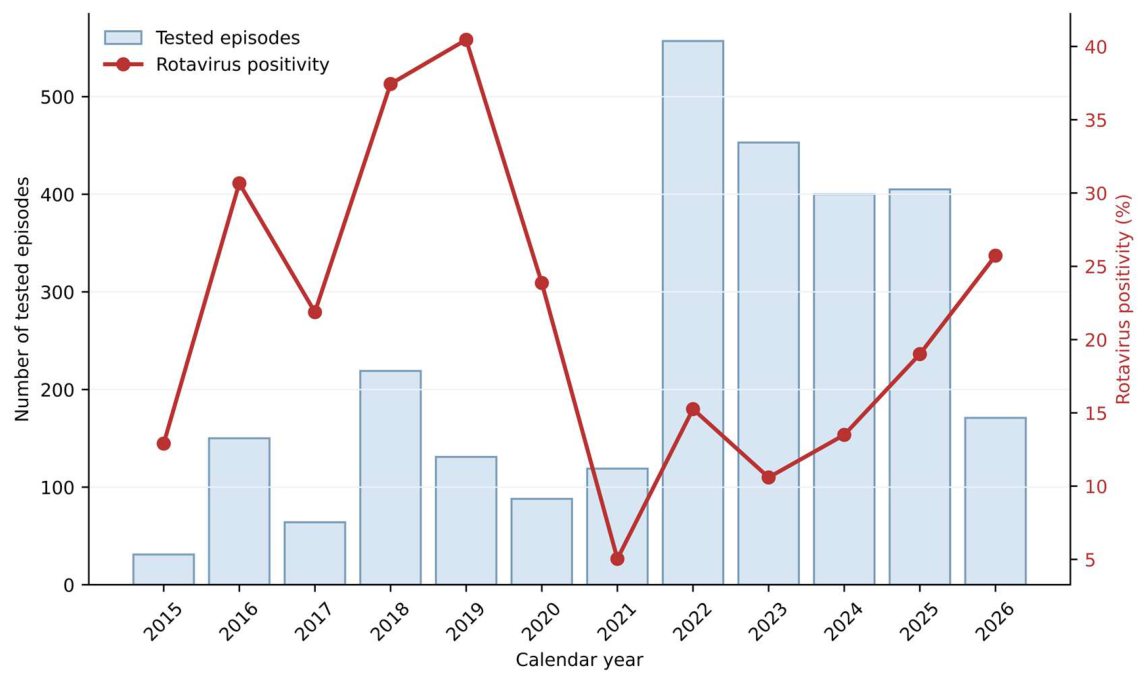
Table 4.
Exploratory calendar-period analyses.
| Calendar period | Episodes | Cases | Vaccinated episodes | Adjusted VE %, (95% CI) | P value |
|---|---|---|---|---|---|
| 2015–2019 | 595 | 199 | 166 | 15.3 (-28.7 to 44.3) | 0.437 |
| 2020–2021 | 207 | 27 | 57 | 35.9 (-105.5 to 80.0) | 0.454 |
| 2022–2026 | 1986 | 308 | 397 | 77.7 (62.3 to 86.8) | <0.001 |
4. Discussion
4.1. Principal Findings
In this 11-year test-negative study of children younger than 5 years, documented complete rotavirus vaccination was associated with a 52.8% reduction in the adjusted odds of laboratory-confirmed rotavirus gastroenteritis. Effectiveness against presentations requiring hospitalization was 57.8%. The main estimate was robust to alternative episode windows, a 14-day post-completion requirement, restriction to the first episode per child, and a more parsimonious temporal model.
The test-negative analysis materially changes the interpretation that would have arisen from studying positive cases alone. Within rotavirus-positive cases, vaccination was not associated with hospitalization after temporal adjustment. Nevertheless, when vaccinated test-negative controls were included, vaccination was associated with substantially lower odds of rotavirus positivity both overall and among hospitalized children. These results illustrate why case-only severity analyses cannot substitute for vaccine-effectiveness designs.
The overall estimate is clinically meaningful and broadly consistent with international real-world evidence. Diallo et al. reported high effectiveness against rotavirus-associated emergency visits and hospitalization over 2009–2022, with the greatest protection against very severe disease [8]. A Turkish study of self-financed vaccination likewise reported reductions in rotavirus-positive gastroenteritis and severe outcomes [10]. The magnitude observed here is lower than estimates from some high-income surveillance systems but lies within the broad range reported across settings [5,6,7,8]. Differences in vaccine coverage, case ascertainment, circulating genotypes, healthcare access, and vaccination-record completeness may contribute.
More specifically, the adjusted overall effectiveness of 52.8% was lower than the 78% effectiveness against rotavirus-associated emergency-department visits or hospitalization reported by Diallo et al. in a United States network [8]. However, estimates vary according to outcome severity and setting. A 2023 test-negative study from Shanghai found strong protection after a complete three-dose pentavalent schedule [17], while a 2024 Spanish real-world cohort of self-financed vaccination estimated 82% direct effectiveness against rotavirus-associated primary-care gastroenteritis [18]. Our lower pooled estimate may reflect inclusion of both outpatient and inpatient presentations, the combination of licensed complete schedules into a single exposure category, differences in age and healthcare-seeking patterns, incomplete capture of vaccination outside the institution, and the unusually long observation window spanning major epidemiological disruption.
4.2. Temporal Heterogeneity
The most important caution is the marked calendar-period variation. No statistically detectable effectiveness was observed during 2015–2019, whereas effectiveness was high during 2022–2026. The pandemic-period estimate was unstable because rotavirus activity was strongly suppressed in 2021 and few cases were available. This heterogeneity means that the pooled estimate should not be interpreted as a constant biological effect across all 11 years.
Several explanations are possible. The COVID-19 pandemic altered pathogen circulation, childcare exposure, healthcare-seeking, testing thresholds, referral pathways, and hospital admission practices. Changes in the mix of rotavirus genotypes could also modify measured effectiveness. In addition, institutional vaccination documentation may have become more complete over time, while vaccination received outside the institution could produce residual misclassification. Recent Turkish data have likewise demonstrated substantial pandemic-associated changes in rotavirus seasonality and clinical presentation [13].
The direction of the period difference cannot be determined from the available variables. The stronger post-pandemic estimate may represent true protection under a changed epidemiological context, improved exposure ascertainment, altered testing selection, or a combination of these factors. Accordingly, the period-specific estimates are best interpreted as exploratory and hypothesis-generating.
Importantly, the absence of statistically detectable effectiveness during 2015–2019 should not be interpreted as evidence that rotavirus vaccination was biologically ineffective in that period. The estimate was imprecise and may have been affected by lower vaccination prevalence, exposure misclassification, unmeasured changes in testing selection, age-related differences, and variation in circulating strains. Conversely, the high estimate during 2022–2026 should not be viewed in isolation as proof of increasing biological effectiveness. Its concordance with recent high-effectiveness estimates is reassuring [8,17,18], but the significant interaction by period indicates that calendar-specific selection and measurement processes remain plausible explanations.
4.3. Strengths
Strengths include a large pool of test-negative controls drawn from the same clinical pathway as cases, deterministic linkage with a completed-vaccination registry, an 11-year observation period, complete age, sex, result, date, and treatment-setting data, and explicit control for calendar year and month. Consolidation of repeat tests reduced nonindependence from serial testing, while child-clustered standard errors addressed multiple distinct episodes. The consistency of the overall estimate across sensitivity analyses supports its statistical robustness.
4.4. Limitations
This study has important limitations. First, vaccination status was ascertained from institutional records. Complete RotaTeq and Rotarix schedules and dose dates were verified, and children in the unvaccinated group were documented as having received no rotavirus vaccine. Nevertheless, vaccination administered outside the institution could have been missed if it was not reported or entered into the record, and residual exposure misclassification cannot be excluded.
Second, the analysis lacked symptom-level information, validated Vesikari severity scores, dehydration grade, intravenous-fluid requirement, length of stay, intensive-care admission, comorbidities, socioeconomic variables, and childcare exposure. Hospitalization is clinically relevant but is also influenced by admission practices and healthcare access.
Third, testing was clinically indicated rather than protocolized. Changes in clinicians’ thresholds for stool testing, laboratory methods, outpatient access, and referral patterns may have altered the composition of cases and controls. Year and month adjustment cannot eliminate all residual temporal confounding.
Fourth, the data did not include circulating rotavirus genotypes. Genotype changes could contribute to period-specific variation.
Fifth, although complete vaccination was defined using the licensed product-specific schedules (three doses for RotaTeq and two doses for Rotarix), the analysis intentionally combined the two complete schedules and therefore could not estimate product-specific effectiveness. The dataset also did not support reliable assessment of individual-dose effects or time since the final dose. This precluded evaluation of whether protection differed by vaccine product or waned with increasing age and time since vaccination. Such information is relevant because meta-regression evidence indicates that the durability of protection can vary across epidemiological settings [19]. Product-specific comparisons would additionally be vulnerable to confounding by calendar time because availability, uptake, documentation, and circulating strains may change concurrently. Sixth, the single-center design limits generalizability. Finally, the study estimates effectiveness among children who presented and were tested; it does not directly estimate protection against all community rotavirus infections.
4.5. Clinical and Research Implications
The results support completion of a licensed rotavirus vaccination course as protection against medically attended and hospitalized rotavirus gastroenteritis in a setting where vaccination has historically been self-financed rather than universally funded. They also demonstrate the value of retaining negative laboratory results for vaccine-effectiveness research. The pooled estimate is most appropriately interpreted as the effectiveness of documented completion of either licensed schedule within this clinical population, rather than as a product-specific or dose-specific effect. Future multicenter studies should link complete national or regional vaccination histories, vaccine product and dose dates, standardized clinical-severity data, and genotype surveillance. Analyses should prespecify age, time-since-vaccination, and calendar-period interactions when long observation windows span major disruptions such as the COVID-19 pandemic.
5. Conclusions
Documented complete rotavirus vaccination was associated with approximately 53% effectiveness against laboratory-confirmed rotavirus gastroenteritis and 58% effectiveness against rotavirus-associated hospitalization among tested children younger than 5 years. Findings were robust across multiple sensitivity analyses. However, effectiveness varied markedly across calendar periods, with no detectable effect before the pandemic and substantially higher effectiveness after 2022. The pooled result therefore supports vaccination while requiring cautious interpretation in light of temporal heterogeneity and the limitations of single-center retrospective data.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Hisar Hospital Medical and Ethics Advisory Board (approval number 26/77).
Informed Consent Statement
Patient consent was waived because of the retrospective design and use of routinely collected, de-identified clinical data. The exact waiver wording must be verified against the ethics decision before submission.
Data Availability Statement
The datasets generated and/or analyzed during the current study are available from the corresponding author upon reasonable request. The data are not publicly available because they contain information that could compromise patient privacy and confidentiality.
Conflicts of Interest
The authors declare that they have no competing interests.
References
- World Health Organization. Rotavirus vaccines: WHO position paper—July 2021. Wkly. Epidemiol. Rec. 2021, 96(28), 301–320. [Google Scholar]
- Ruiz-Palacios, G.M.; Pérez-Schael, I.; Velázquez, F.R.; et al. Safety and efficacy of an attenuated vaccine against severe rotavirus gastroenteritis. N Engl. J. Med. 2006, 354, 11–22. [Google Scholar] [CrossRef] [PubMed]
- Vesikari, T.; Matson, D.O.; Dennehy, P.; et al. Safety and efficacy of a pentavalent human–bovine (WC3) reassortant rotavirus vaccine. N Engl. J. Med. 2006, 354, 23–33. [Google Scholar] [CrossRef] [PubMed]
- Linhares, A.C.; Velázquez, F.R.; Pérez-Schael, I.; et al. Efficacy and safety of an oral live attenuated human rotavirus vaccine during the first 2 years of life in Latin American infants. Lancet 2008, 371, 1181–1189. [Google Scholar] [CrossRef] [PubMed]
- Sun, Z.; Fu, Y.; Lu, H.; Bie, P.; Wu, Q. Association of rotavirus vaccines with reduction in rotavirus gastroenteritis in children younger than 5 years: a systematic review and meta-analysis. JAMA Pediatr. 2021, 175, e210347. [Google Scholar] [CrossRef] [PubMed]
- Burnett, E.; Parashar, U.D.; Tate, J.E. Global impact of rotavirus vaccination on diarrhea hospitalizations and deaths among children younger than 5 years: 2006–2019. J. Infect. Dis. 2020, 222, 1731–1739. [Google Scholar] [CrossRef] [PubMed]
- Adlhoch, C.; Höhne, M.; Littmann, M.; et al. Rotavirus vaccine effectiveness and risk factors for breakthrough infections in Germany, 2010–2011. Pediatr. Infect. Dis. J. 2013, 32, e82–e89. [Google Scholar] [CrossRef] [PubMed]
- Diallo, A.O.; Wikswo, M.E.; Sulemana, I.; et al. Rotavirus vaccine effectiveness against severe acute gastroenteritis: 2009–2022. Pediatrics 2024, 154, e2024066879. [Google Scholar] [CrossRef] [PubMed]
- Ceyhan, M.; Alhan, E.; Salman, N.; et al. Multicenter prospective study on the burden of rotavirus gastroenteritis in Turkey, 2005–2006. J. Infect. Dis. 2009, 200 Suppl 1, S234–S238. [Google Scholar] [CrossRef] [PubMed]
- Gönüllü, E.; Soysal, A.; Yıldız, İ.; Karaböcüoğlu, M. Impact of self-financed rotavirus vaccination on acute gastroenteritis in young children in Turkey. Hum. Vaccin Immunother. 2021, 17, 510–516. [Google Scholar] [CrossRef] [PubMed]
- Tate, J.E.; Patel, M.M.; Cortese, M.M.; et al. Use of patients with diarrhea who test negative for rotavirus as controls to estimate rotavirus vaccine effectiveness through case-control studies. Clin. Infect. Dis. 2016, 62 Suppl 2, S106–S114. [Google Scholar] [CrossRef] [PubMed]
- Payne, D.C.; Selvarangan, R.; Azimi, P.H.; et al. Association of rotavirus vaccination with inpatient and emergency department visits among children seeking care for acute gastroenteritis, 2010–2016. JAMA Netw. Open 2019, 2, e1912242. [Google Scholar] [CrossRef] [PubMed]
- Öztelcan Gündüz, B.; Kutlutürk, K.; Ünay, B. Rotavirus infections in the pediatric population: a comparative study of pre-COVID and COVID-19 pandemic periods. Front Public Health 2025, 13, 1495848. [Google Scholar] [CrossRef] [PubMed]
- Burnett, E.; Parashar, U.D.; Winn, A.; Tate, J.E. Trends in rotavirus laboratory detections before and after rotavirus vaccine introduction and in the context of the COVID-19 pandemic—United States, 2000–2021. J. Infect. Dis. 2022, 226, 967–974. [Google Scholar] [CrossRef] [PubMed]
- Gascó-Laborda, J.C.; Tirado-Balaguer, M.D.; Gil-Fortuño, M.; et al. Impact of the pandemic on infectious diseases with different epidemiological patterns. Rev. Esp. Salud Publica 2024, 98, e202402011. [Google Scholar] [PubMed]
- von Elm, E.; Altman, D.G.; Egger, M.; et al. The Strengthening the Reporting of Observational Studies in Epidemiology statement. Lancet 2007, 370, 1453–1457. [Google Scholar] [CrossRef] [PubMed]
- Ma, W.; Wei, Z.; Guo, J.; et al. Effectiveness of pentavalent rotavirus vaccine in Shanghai, China: a test-negative design study. J. Pediatr. 2023, 259, 113461. [Google Scholar] [CrossRef] [PubMed]
- López-Lacort, M.; Muñoz-Quiles, C.; Díez-Domingo, J.; Orrico-Sánchez, A. Effectiveness of self-financed rotavirus vaccines on acute gastroenteritis primary care episodes using real-world data in Spain: a propensity score-matched analysis of cohort study. Eur. J. Pediatr. 2024, 183, 2579–2588. [Google Scholar] [CrossRef] [PubMed]
- Clark, A.; van Zandvoort, K.; Flasche, S.; et al. Efficacy of live oral rotavirus vaccines by duration of follow-up: a meta-regression of randomised controlled trials. Lancet Infect. Dis. 2019, 19, 717–727. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Study flow diagram showing source test records, episode consolidation, and the final test-negative analytical cohort.
Figure 1.
Study flow diagram showing source test records, episode consolidation, and the final test-negative analytical cohort.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.