
Submitted:
01 October 2026
Posted:
02 October 2026
Read the latest preprint version here
Abstract
Nicotinamide adenine dinucleotide (NAD⁺/NADH) metabolism occupies a central position in both tumour pathogenesis and cellular aging. Current therapeutic strategies pursue apparently contradictory objectives: oncology seeks to deplete NAD⁺ in cancer cells, while anti-aging practice administers NAD⁺ intravenously to restore levels that decline with age. This work proposes the pulsed imposition of a reductive load as an integrated anti-cancer and anti-aging strategy. The core proposition concerns a kinetic condition rather than any specific molecular vehicle: reducing equivalents arising faster than the cell can dispose of them. Where the respiratory chain retains proton-pumping capacity, that load produces a more specific thermodynamic state — over-reduction of the mitochondrial coenzyme Q pool sustained at elevated membrane potential — and because under normoxic operation the pool receives electrons from several dehydrogenases while discharging them through a single oxygen-dependent outlet, that state is reachable in two directions: addition of the electron donor, or subtraction of the terminal acceptor. Where proton-pumping capacity is compromised the same load instead limits free NAD⁺ as electron acceptor, in two compartmentally distinct arms that the two routes do not reach equivalently. NADH is discussed as the illustrative first-line donor because it is the native substrate of the respiratory chain and has an existing clinical precedent for intravenous administration, but it is explicitly not the ideal vehicle, being limited by molecular instability, restricted membrane permeability and stoichiometric consumption. A second class of donor, entering at or below the quinone pool rather than through the pyridine nucleotide pools, is identified; the sulfide couple is the endogenous case, and is notable in performing both directions of intervention with one species. Selectivity is proposed to arise from differential redox buffering capacity between healthy and transformed cells, through two complementary mechanisms: reverse electron transport at Complex I in cells retaining proton-pumping capacity, and limitation of free NAD⁺ in cells that cannot re-oxidise NADH, arresting mitochondrial substrate-level phosphorylation in the matrix and glycolysis in the cytosol. The origin of selectivity differs between routes — metabolic under donor addition, perfusional and spatial under acceptor subtraction — so that the two have largely disjoint zones of resistance and are complementary in domain as well as multiplicative in magnitude. Healthy cells are proposed to escape both by possessing simultaneously the respiratory reserve to dispose of the imposed load and the gradient-discharging flux required to discharge the accumulated proton gradient. A protocol of brief, intense pulses followed by recovery phases (redox press-pulse) is proposed, in combination with glucose restriction and optimisation of intracellular magnesium. The framework generates dissociable experimental signatures, an explicitly predicted zone of resistance, and a candidate predictive biomarker. Principal limitations, including cytosolic lactate dehydrogenase and mitochondrial proton leak as escape routes and the vulnerability of cardiac and neural tissue to the same reverse-electron-transport mechanism, are stated explicitly.
Keywords:
reductive load
; reverse electron transport
; Warburg effect
; redox impulses
; cancer metabolic therapy
; anti-aging
; mitochondrial membrane potential
; NAD⁺/NADH
; press-pulse
; reducing equivalents
; acceptor subtraction
; electrochemical
; hydrogen sulfide
; sulfide:quinone oxidoreductase
; NADH
1. Introduction
Cancer and aging share deep metabolic roots that converge on mitochondrial metabolism and cellular redox homeostasis. Despite decades of research, these two conditions have been addressed as separate entities, with therapeutic strategies often in mutual contradiction. Metabolic oncology, inspired by the pioneering work of Otto Warburg (1, 1b) and recently revisited by Thomas Seyfried (2), identifies mitochondrial dysfunction as the fundamental characteristic of cancer cells. Molecular gerontology, on the other hand, recognises the decline in mitochondrial function and NAD⁺ depletion as two central hallmarks of aging (3, 4).
This work proposes a unifying theoretical framework based on pulsed manipulation of the NAD⁺/NADH redox state as a simultaneously anti-cancer and anti-aging strategy. Unlike current practices — which predominantly administer NAD⁺ (oxidised form) intravenously in anti-aging clinics (5), or aim to deplete NAD⁺ in cancer cells through NAMPT inhibitors in oncology (6) — the administration of exogenous reducing equivalents, with NADH (reduced form) as the illustrative vehicle, in brief and intense cyclic pulses is proposed here.
A clarification of scope is warranted at the outset, since the terminology has proved open to misreading, and a distinction must be drawn on which the remainder of this work depends. The intervention proposed here consists in acutely and transiently imposing a load of reducing equivalents in excess of the rate at which the cell can dispose of it, followed by a recovery phase, repeated cyclically. That is the intervention, and it is one thing. What it produces is two things, and which of them obtains is determined by the cell rather than by the operator.
In a cell whose respiratory chain retains proton-pumping capacity, the load raises the reduction state of the mitochondrial coenzyme Q pool while membrane potential remains high. This is a specific thermodynamic state, distinct from the load that produced it, and it is the state that permits reverse electron transport at Complex I (Mechanism A, Section 5.1.1). Two routes reach it, since the pool has multiple inputs and, under normoxic operation, a single outlet: increasing electron input at any of the dehydrogenases that reduce it — Complexes I and II, and also electron-transfer flavoprotein–ubiquinone oxidoreductase, mitochondrial glycerol-3-phosphate dehydrogenase, dihydroorotate dehydrogenase and proline dehydrogenase — which is the pharmacological route developed in Section 5.5 and Section 6, or closing the outlet by limiting oxygen availability at Complex IV, which is the electrochemical route developed in Section 5.6 and Section 8.2(j). For this state, and for this state alone, the two directions are interchangeable, and the mechanism that follows is indifferent to which produced it.
In a cell whose chain cannot re-oxidise NADH at a sufficient rate, the same load does not produce that state, since the potential is not sustained. Its consequence is instead limitation of free NAD⁺ as an electron acceptor, and this occurs in two compartments that are not equivalent. In the matrix, where the only significant outlet is Complex I, the arrest is reached by either route, to a degree set by residual NAD⁺ regeneration, and cytosolic lactate dehydrogenase cannot oppose it. In the cytosol, where lactate dehydrogenase regenerates NAD⁺ without mitochondrial participation, it is reached by delivery of reducing equivalents or by withdrawal of pyruvate as the cytosolic acceptor, and not by withdrawal of oxygen at any intensity.
What the two mechanisms share is therefore the imposed load and the phenotypic plane along which they are distributed, and not a single thermodynamic condition. A further consequence, developed in Section 5.1.1, is that the two routes do not fail in the same places: donor addition is escaped where the chain retains respiratory reserve, acceptor subtraction where perfusion restores the terminal acceptor, and these regions are largely disjoint. Their combination is accordingly complementary in domain and not only multiplicative in magnitude.
NADH is presented throughout as an illustrative vehicle for the first route rather than an optimal one. Its advantages are that it is the native substrate of the respiratory chain, that it is recognised directly by the relevant dehydrogenases, and that intravenous administration is technically established with existing clinical precedent (7, 8). Its disadvantages are substantial: limited permeability across the plasma membrane, molecular instability in plasma, and stoichiometric rather than catalytic consumption. As discussed in Section 6.2, ubiquinol, ketone-body clamps and prospective catalytic redox systems address different subsets of these limitations.
The rationale rests on three pillars: (i) the intrinsic metabolic selectivity of exogenous reducing equivalents, which exploits the difference in mitochondrial competence between healthy and cancer cells; (ii) the pulse logic (redox press-pulse), derived from Seyfried’s therapeutic strategy (9) and the physiology of radiation fractionation; (iii) the convergence between the mechanisms activated by cyclic reductive impulses (autophagy, mitophagy, inflammation reduction, mitochondrial turnover) and the well-known anti-aging pathways (sirtuins, AMPK, mTOR).
It is important to emphasise that, although some clinics already use NADH infusions — notably the Hyperthermia Centre Hannover in the oncological setting (8) and Birkmayer’s clinical studies for Parkinson’s disease (7, 89) — none of these precedents has articulated the metabolic selectivity rationale proposed here, the press-pulse logic applied to redox state, the synergistic combination with glucose restriction, or the unifying anti-cancer/anti-aging framework.
Two Supplementary Materials are appended to this work. Supplementary Material S1 develops the differential response of healthy and transformed cells across the loading and recovery phases of the cycle, and identifies the parameter that determines discharge of the proton gradient. Supplementary Material S2 provides a quantitative estimate of the cathodic alkalinisation constraint governing the electrochemical implementation of acceptor subtraction, together with its translation into electrode parameters. Neither is required for the argument that follows; both are cited at the points where the corresponding question arises and appear at the end of the work.
2. The Warburg Effect and Tumour Metabolism: The Central Role of NAD⁺/NADH
2.1. Glycolytic Dependence of Cancer Cells
In the 1920s, Otto Warburg observed (1) that cancer cells prefer glycolysis followed by lactic fermentation even in the presence of sufficient oxygen for oxidative phosphorylation — a phenomenon known as aerobic glycolysis or the Warburg effect. This observation, initially interpreted as a simple metabolic adaptation, has been reinterpreted by Seyfried as evidence of a primary mitochondrial dysfunction that forces the cell to depend on fermentation for ATP production (2).
In this context, NAD⁺ plays a critical and dual role. On one hand, glycolysis requires NAD⁺ as a cofactor in the reaction catalysed by glyceraldehyde-3-phosphate dehydrogenase (GAPDH). To maintain glycolytic flux, the cancer cell must constantly regenerate NAD⁺ from NADH, primarily through the conversion of pyruvate to lactate by lactate dehydrogenase (LDH) (10). On the other hand, NAD⁺ serves as a substrate for enzymes critical to tumour survival, including PARP (DNA repair), sirtuins (gene expression regulation), and CD38/CD157 (signaling) (11).
Recent work has revealed a third, previously underappreciated source of ATP in cancer cells: mitochondrial substrate level phosphorylation (mSLP) through the glutaminolysis pathway (12, 13). Cancer cells can produce significant ATP at the succinyl-CoA ligase reaction, using glutamine as fuel via the sequence glutamine → glutamate → α-ketoglutarate → succinyl-CoA → succinate + ATP/GTP. Succinate and lactate, as end-products of glutamine and glucose fermentation respectively, together acidify the tumour microenvironment (12). Importantly, neither oxygen consumption nor lactate production are accurate markers for ATP production through OxPhos or glycolysis in cancer cells (12, 13). The mSLP pathway is critically relevant to the hypothesis presented here because the α-ketoglutarate dehydrogenase reaction — upstream of succinyl-CoA ligase — requires NAD⁺ as an electron acceptor, making it vulnerable to the same NAD⁺ depletion mechanism that blocks glycolysis.
2.2. The NAD⁺ Paradox in Oncology vs Anti-Aging
Recent oncological literature has clearly identified NAD metabolism as a therapeutic target, demonstrating that the enzyme NAMPT (nicotinamide phosphoribosyltransferase), rate-limiting for NAD synthesis, is frequently amplified in various cancer types (6, 14). NAMPT inhibitors such as FK866 effectively deplete NAD and suppress tumour proliferation (15).
This creates a paradox that has received insufficient discussion: systemic administration of NAD⁺ may supply the glycolytic metabolism of subclinical neoplastic clones with the cofactor required by GAPDH and LDH, and may additionally support PARP-mediated DNA repair and sirtuin activity in those cells. The exposed population is the one in which this concern is least reassuring, since intravenous NAD⁺ and its precursors are administered predominantly to individuals in the age range of highest prevalence of undiagnosed occult neoplasia. The counter-consideration is that NAD⁺ also supports immune function and genomic maintenance in healthy tissue, and the preclinical literature on NAD⁺ precursors in tumour models is not univocal. No epidemiological signal of increased incidence has been reported to date, although population-scale exposure is recent and no oncological surveillance accompanies it. The position taken here is that the question is open rather than settled, and that it warrants investigation independently of the therapeutic hypothesis advanced in this work.
2.3. Exogenous Reducing Equivalents vs NAD⁺: A Fundamental Distinction
This work proposes that the administration of reducing equivalents — taking NADH (reduced form) as the illustrative case — produces radically different metabolic effects from the administration of NAD⁺ (oxidised form). While NAD⁺ fuels tumour glycolysis by providing the necessary oxidising cofactor, an acute excess of NADH creates the opposite conditions: it saturates the cellular NADH/NAD⁺ ratio, reducing the availability of free NAD⁺ and blocking glycolysis due to the lack of an electron acceptor at GAPDH. The consequences that follow depend on residual mitochondrial competence, as set out in Section 5.1.1 (Figure 1). The asymmetry has a structural basis. An excess of NADH has a dedicated high-capacity outlet in the respiratory chain, regulated by respiratory control; an excess of NAD⁺ has no equivalent reductive outlet, since dehydrogenases reduce it only where oxidisable substrate is available. The enzymes that consume NAD⁺ — CD38, PARP, sirtuins — hydrolyse rather than reduce it, so disposal proceeds by degradation rather than by recycling.
The principle is not limited to NADH alone. Any delivery modality that acutely increases the intracellular load of reducing equivalents — exogenous NADH, ubiquinol, dissolved molecular hydrogen, or catalytic redox systems — could produce analogous effects, provided the perturbation is sufficiently rapid and intense to exceed the compensatory capacity of cancer cells without exceeding that of healthy cells.
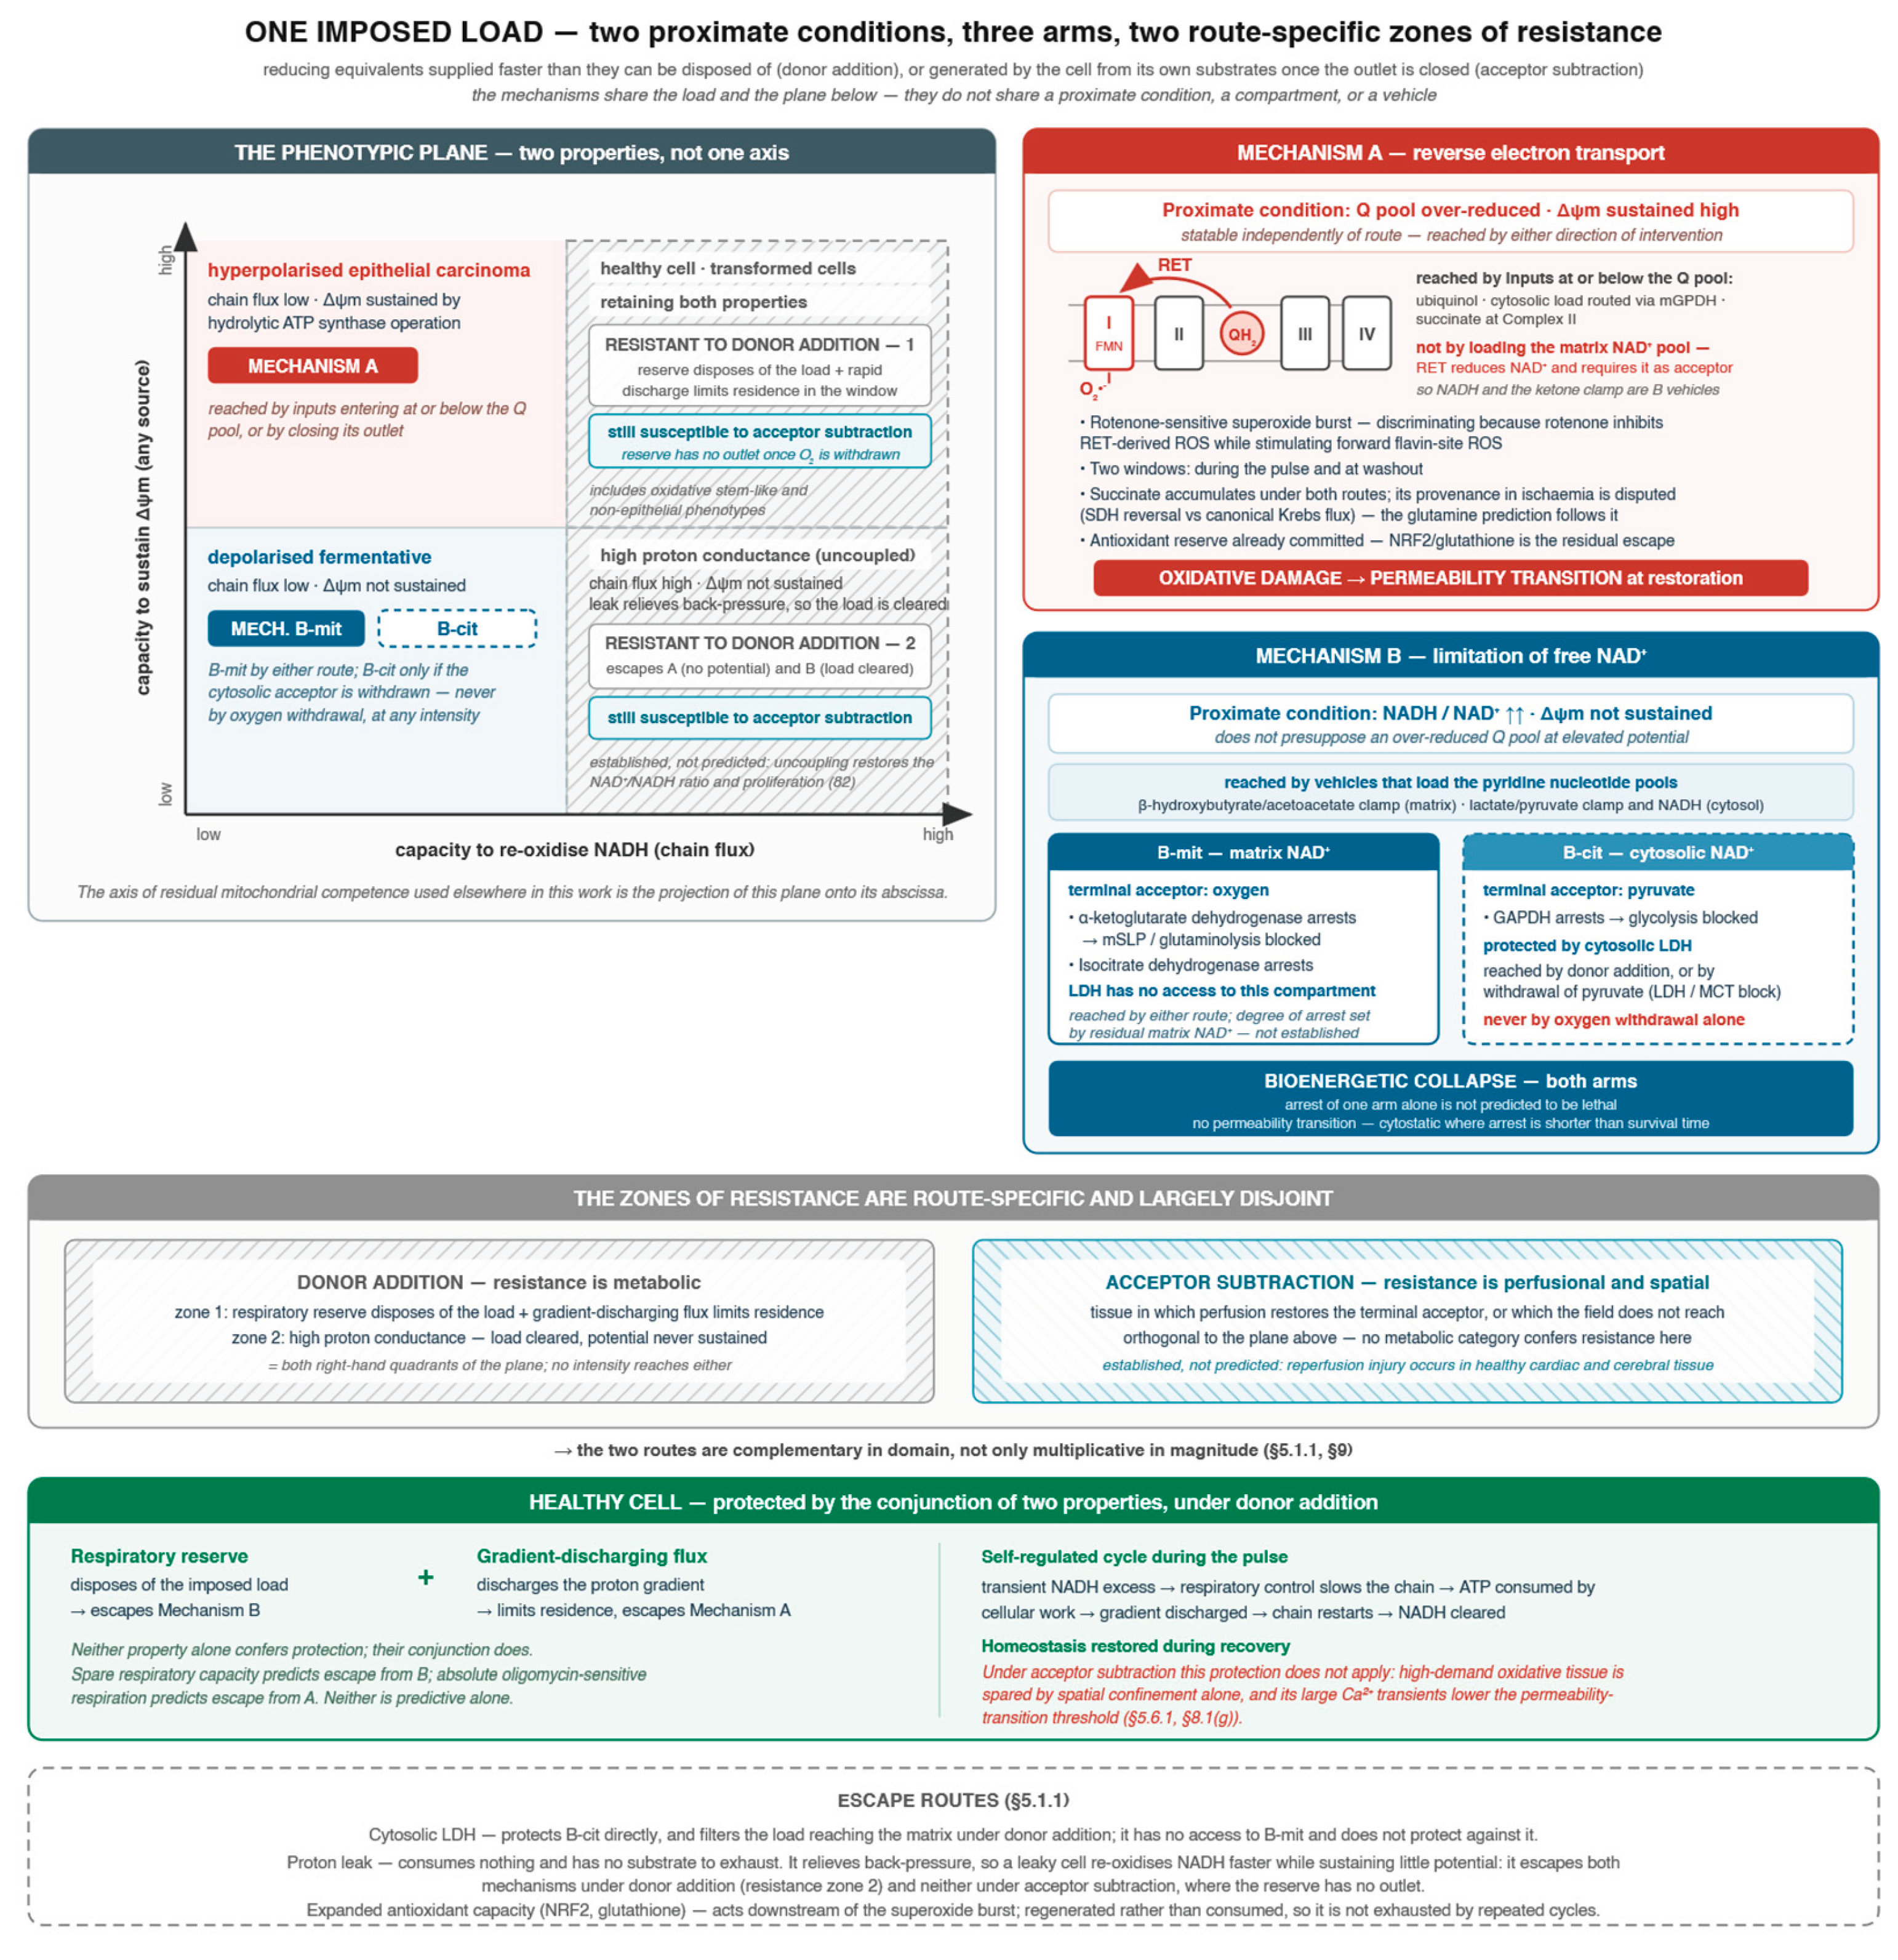
Figure 1.
A single imposed reductive load, two proximate conditions, and two route-specific zones of resistance. The mechanisms share the imposed load and the phenotypic plane shown, not a proximate condition. Mechanism A requires an over-reduced coenzyme Q pool at sustained elevated membrane potential and is reached by either direction of intervention. Mechanism B requires limitation of free NAD⁺ and has two compartmentally distinct arms: the mitochondrial arm, whose terminal acceptor is oxygen and which cytosolic lactate dehydrogenase cannot oppose, and the cytosolic arm, whose terminal acceptor is pyruvate and which oxygen withdrawal does not reach at any intensity. The two properties plotted are independent, since membrane potential may be sustained by hydrolytic ATP synthase operation in the absence of chain flux; the axis of residual mitochondrial competence used elsewhere in this work is the projection of this plane onto its abscissa. The zones of resistance differ by route — metabolic under donor addition, perfusional and spatial under acceptor subtraction — and are largely disjoint, which is the basis of the complementarity in domain set out in Section 5.1.1 and Section 9. Note: Two zones of resistance to donor addition are shown rather than one: the upper-right quadrant, where competence is retained, and the lower-right, where high proton conductance clears the load without sustaining potential. Neither survives withdrawal of the terminal acceptor.
3. Redox State and Tumour Microenvironment
3.1. The Oxidative-Inflammatory Environment as a Tumour Substrate
Cancer cells maintain an elevated but controlled level of reactive oxygen species (ROS), which serves as a proliferative signal through the constitutive activation of HIF-1α, NF-κB, and mTOR (16). Chronic inflammation in the tumour microenvironment generates additional ROS through macrophages, neutrophils, and cancer-associated fibroblasts (CAFs), creating a self-reinforcing cycle: inflammation → ROS → mitochondrial damage → greater dependence on glycolysis → lactate production → microenvironment acidification → immunosuppression → further inflammation (17). The position of acidification within that cycle should be stated precisely, since it bears on what the framework does and does not propose to correct. Extracellular acidity is an output of fermentative metabolism rather than a terrain from which transformation arises, and the intracellular pH of transformed cells is maintained alkaline by the same export that acidifies the exterior. Correcting extracellular acidity is therefore not proposed here as a therapeutic objective, and would in fact facilitate proton-coupled lactate export and thereby cytosolic NAD⁺ regeneration (Section 5.1.1). The framework exploits acidification rather than reversing it: the intracellular acidosis that follows blocked export is a component of the cytosolic arm of Mechanism B, and the reduction of chronic oxidative and inflammatory load discussed in Section 7.1 concerns reactive species rather than pH. The two are independent variables and are treated separately throughout.
In this context, the NAD⁺/NADH ratio is a critical indicator of intracellular redox state. Cancer cells tend to maintain a high NAD⁺/NADH ratio through intense LDH activity, which regenerates NAD⁺ at the expense of NADH (10). Acute perturbations of this ratio — specifically, a sudden increase in intracellular NADH — destabilise tumour metabolism at multiple levels.
3.2. The Transmembrane Redox Interface
A legitimate objection to the manipulation of extracellular redox state is that the cell membrane could isolate the intracellular compartment. Several routes of transmembrane redox communication have been documented and are listed below; as noted in (e), not all prove redox-sensitive on closer examination:
- (a)
- Transplasma membrane redox systems (ECTO-NOX): membrane proteins that transfer electrons from intracellular NADH to extracellular acceptors; in a reduced external environment, these systems are blocked, causing intracellular NADH accumulation (18).
- (b)
- Cysteine/cystine system (xCT/SLC7A11): the xCT transporter imports cystine (oxidised form), which is internally reduced to cysteine for glutathione synthesis. A reductive extracellular environment alters the cysteine/cystine ratio, modifying the intracellular glutathione pool (19).
- (c)
- Redox-sensitive receptors: EGFR, IGFR, and integrins possess extracellular domains with cysteine residues whose oxidation is required for dimerization and activation. A reductive environment suppresses these proliferative signals (20).
- (d)
- Direct ROS diffusion: hydrogen peroxide (H₂O₂) crosses the cell membrane, including through aquaporins, acting as a transmembrane redox messenger (21).
- (e)
- Lactate/pH gradients: lactate transport through MCT1 and MCT4 is a proton-coupled process governed by the substrate concentration gradient and the proton motive force (22). It is not directly sensitive to the redox potential of the extracellular medium; any influence of a reductive impulse on this route would be indirect, mediated by changes in metabolic flux and consequent shifts in extracellular pH. On thermodynamic grounds the effect would in fact run in the opposite direction: a reductive load shifts the LDH equilibrium toward lactate, raising intracellular lactate and thereby increasing rather than reducing the outward gradient. Blockade of lactate export, which would drive the LDH reaction toward equilibrium and arrest cytosolic NAD⁺ regeneration (54, 57), therefore requires pharmacological inhibition rather than redox saturation, and is complicated by documented autoregulation of H⁺/lactate efflux under MCT inhibition (58).
- (f)
- Connexin hemichannels: undocked connexin 43 hemichannels, distinct from the docked channels forming intercellular gap junctions, open onto the extracellular space and mediate bidirectional transmembrane fluxes of NAD⁺ in intact cells (23, 53). Open hemichannels also permit passage of lactate, glutathione and ATP, and their opening probability is increased by an intracellular reducing redox potential. Their direction of flux is set by the transmembrane gradient, so a reducing extracellular environment is expected to modulate, though not abolish, this route.
3.3. Reductive Stress: A Mirror Concept to Oxidative Stress
Reductive stress — defined as an excess of reducing equivalents relative to the system’s capacity to dispose of them — is a real and documented phenomenon, although less studied than oxidative stress (24). Under conditions of NADH excess, the respiratory chain becomes saturated and electrons “leak” from complexes I and III, reacting directly with molecular oxygen to form superoxide. Paradoxically, a reductive excess generates secondary oxidative stress (25).
However, this paradoxical response is proportional to mitochondrial competence: cells with functional mitochondria manage a moderate and transient NADH excess by increasing flux through the respiratory chain and ATP production, with minimal ROS generation. Cells that cannot compensate suffer either glycolytic blockade through NAD⁺ shortage or oxidative damage through reverse electron transport, depending on their residual proton-pumping capacity; the two outcomes and the axis along which they are distributed are set out in Figure 1, and their evolution across successive pulse and recovery phases in Figure 2.
4. Limitations of Conventional Antioxidants
4.1. Lack of Targeting
Classical exogenous antioxidants (vitamin C, vitamin E, beta-carotene) distribute uniformly in body fluids without selectively concentrating at sites of greatest oxidative stress or in the tumour microenvironment (26). This dilution drastically limits their local efficacy.
4.2. Secondary Pro-Oxidation
An antioxidant that donates its electron itself becomes a radical, but in the case of ascorbate the pro-oxidant chemistry originates in the reduced rather than in the oxidised form, and the distinction bears directly on Section 8.2(k). Ascorbate is a one-electron reductant of transition metals as well as a scavenger: in the presence of catalytically available iron — abundant in the tumour microenvironment — it reduces Fe³⁺ to Fe²⁺ and, through autoxidation, supplies the hydrogen peroxide with which Fe²⁺ then generates hydroxyl radical (OH•), the most damaging of the reactive species (27, 85). Its oxidised products, the ascorbate radical and dehydroascorbate, are comparatively unreactive, which is the basis of the position ascorbate occupies in the pecking order of biological reductants (85). Oxidised vitamin E (tocopheryl radical) can propagate lipid peroxidation in membranes if not rapidly regenerated (28). The same inversion holds at pharmacological concentrations of ascorbate, where extracellular hydrogen peroxide generation with the ascorbate radical as intermediate is the accepted mechanism of selective cytotoxicity toward tumour cells (83, 84), which is to say that the best-documented anticancer action of the compound is pro-oxidant rather than reductive. The consequence for this framework is stated here rather than deferred: the objection applies to any administered reductant that transfers single electrons to metal centres, and the vehicles proposed in Section 6.2 escape it not because they are weaker reductants but because they are oxidised enzymatically, by dehydrogenases with defined substrate specificity, rather than by free-radical chemistry with adventitious acceptors. This paradoxical pro-oxidation mechanism at least partially explains the negative results of large clinical trials with antioxidants: the ATBC study showed increased tumours in the beta-carotene group (29), the SELECT study revealed increased prostate cancer risk with vitamin E (30).
4.3. Inadequate Compartmentalization
Critical oxidative damage occurs predominantly in the inner mitochondrial membrane, where the respiratory chain transfers electrons. Vitamin C, being water-soluble, does not penetrate lipid membranes effectively; vitamin E, being lipid-soluble, distributes in membranes but does not selectively concentrate in mitochondria (31). Targeted mitochondrial antioxidants such as MitoQ and SkQ1, conjugated with lipophilic cations that exploit the mitochondrial membrane potential, represent an advancement but do not solve the stoichiometry problem: they are consumed after donating one electron (32).
4.4. The Advantage of Reducing Equivalents as Electron Vehicles
The administration of reducing equivalents, of which NADH is the illustrative case, overcomes the three limitations of conventional antioxidants: (i) it does not require artificial targeting because selectivity emerges from the difference in mitochondrial competence between healthy and cancer cells; (ii) NADH is the native substrate of the respiratory chain, not an exogenous agent; (iii) it operates at the central metabolic system level (Krebs cycle, respiratory chain) rather than as a peripheral ROS scavenger. Other forms of exogenous electronic delivery — ubiquinol, molecular H₂, catalytic metalloporphyrins — share advantage (i) while differing in site of action and specific mechanism.
The comparison in this section concerns administered molecules. The acceptor-subtraction route of Section 5.6 is not subject to any of the three limitations above, since nothing is delivered: it requires neither targeting, nor a vehicle that becomes a radical upon electron donation, nor stoichiometric replacement, the reducing load being generated by the cell’s own substrates.
5. Hypothesis: Cyclic Reductive Impulses via Exogenous Reducing Equivalents
5.1. Rationale for Intrinsic Metabolic Selectivity
The selectivity of the proposal is based on a fundamental biological asymmetry: the difference in mitochondrial competence between healthy and cancer cells.
In a healthy cell, an acute reductive load is handled by the respiratory chain. The route by which it reaches the chain depends on the vehicle (Section 5.5): a delivered substrate is oxidised intracellularly by the relevant dehydrogenase, and the resulting NADH reaches the matrix pyridine nucleotide pool through the malate-aspartate shuttle, while the glycerol-phosphate shuttle delivers the equivalents directly to the coenzyme Q pool, bypassing Complex I. Under acceptor subtraction no delivery occurs at all and the load arises from the cell’s own substrates (Section 5.6). However it arises, the load is discharged through the same outlet: matrix NADH is oxidised at Complex I, electrons reach the quinone pool and flow through Complexes III and IV to oxygen, generating a proton gradient that powers ATP synthase. However, it is essential to consider the mechanism of respiratory control: when intracellular ATP reaches high levels, the increased ATP/ADP ratio inhibits ATP synthase; the proton gradient accumulates on the inner mitochondrial membrane; the respiratory chain slows due to the inability to discharge the gradient; complex I accepts fewer electrons from NADH (33). This physiological feedback mechanism prevents the healthy cell from oxidising NADH indefinitely — a regulated ceiling exists. The NADH excess accumulates transiently but is subsequently cleared as ATP is consumed by cellular functions. The net result is a self-regulated cycle: transient NADH excess → chain slowdown → ATP consumption → chain restart → NADH clearance. During this process, ROS generation is contained by endogenous antioxidant systems (glutathione, thioredoxin, superoxide dismutase, catalase). A fourth disposal route operates alongside Complex I oxidation, the shuttles and cytosolic LDH, and differs from all three in its dependency. Nicotinamide nucleotide transhydrogenase converts NADH to NADPH at the expense of the proton gradient, sustaining glutathione regeneration, and requires an elevated membrane potential to do so. It is therefore the only route favoured rather than suppressed by the conditions the impulse creates, and it operates in precisely those cells that sustain the gradient — including the hyperpolarised phenotype in which Mechanism A is most favoured (Supplementary Material S1).
In a cell with predominantly fermentative metabolism the same reductive pulse produces an initially similar response: the chain slows, Complex I accepts progressively fewer electrons, and the routes in series with it close, as they do in the healthy cell. The difference is one of degree during loading — a smaller total load and a displaced rather than saturated quinone pool in the healthy cell — and becomes qualitative only on restoration, when the healthy cell discharges the gradient through ATP synthase turnover and reopens the mitochondrial routes, whereas the fermentative cell does not. The reductive load therefore accumulates rather than being disposed of, and the NADH/NAD⁺ ratio shifts sharply toward the reduced state. Supplementary Material S1 sets out the four asymmetries documentable in this phase and the structurally different course that restoration takes in the two populations. Section 5.1.1 sets out the two distinct bioenergetic configurations that follow, depending on residual proton-pumping capacity; the consequences listed below correspond to the configuration in which that capacity is compromised:
- (a)
- Glycolytic blockade: NAD⁺ shortage arrests GAPDH, blocking glycolysis — the primary source of ATP for the cancer cell.
- (b)
- Blockade of mitochondrial substrate level phosphorylation (mSLP): the α-ketoglutarate dehydrogenase reaction, which converts α-ketoglutarate to succinyl-CoA in the glutaminolysis pathway, requires NAD⁺ as an electron acceptor. The depletion of NAD⁺ caused by NADH accumulation blocks this reaction, cutting off the substrate supply to succinyl-CoA ligase and halting mSLP-derived ATP production (12, 13). This means that the cancer cell cannot use glutamine as an alternative energy source to bypass the glycolytic blockade.
- (c)
- Metabolic congestion: NADH excess allosterically inhibits key Krebs cycle enzymes (isocitrate dehydrogenase, α-ketoglutarate dehydrogenase), halting intermediary metabolism.
- (d)
- ROS generation: where residual proton-pumping capacity permits, excess electrons over-reduce the coenzyme Q pool and drive reverse electron transport at Complex I, generating superoxide that the cancer cell — already with antioxidant systems at their limit — cannot neutralise (Section 5.1.1, Mechanism A). Where that capacity is absent, ROS generation is correspondingly modest and cell death follows bioenergetic collapse instead.
- (e)
- Bioenergetic collapse: without ATP from glycolysis, without functional oxidative phosphorylation, and without mSLP from glutaminolysis, the cancer cell undergoes a total energy crisis with consequent plasma membrane depolarisation and activation of cell death pathways. The cancer cell is thus subjected to a simultaneous blockade of all three known ATP-generating pathways.
Of these consequences, (a) presupposes that cytosolic NAD⁺ regeneration has been outpaced, whereas (b) and (c) depend only on arrest of matrix NAD⁺ re-oxidation and arise independently of it. The conditions under which each occurs, and the routes by which they are reached, are set out in Section 5.1.1.
5.1.1. Mechanisms, Compartments, and the Phenotypic Plane
The selectivity mechanism proposed here should be contextualised against the unresolved debate on the quantitative role of oxidative phosphorylation in cancer cells. The mitochondrial metabolic theory of cancer, as consolidated by Seyfried and colleagues (2, 12, 13), holds that tumour cells depend on fermentative glycolysis and glutaminolysis-driven mSLP for ATP production. A parallel line of research, exemplified by Weiss-Sadan et al. (34), describes tumour subsets — such as KEAP1-mutant cells in which NRF2-driven upregulation of ALDH3A1 depletes the NAD⁺ pool — that exhibit selective vulnerability to Complex I inhibition. Rather than claiming validity irrespective of how this dispute is resolved, the framework proposed here makes different and distinguishable predictions depending on where a given tumour sits on the phenotypic plane set out below.
A pulsed reductive load acts through mechanisms that are complementary rather than alternative. What they share is the imposed load itself — reducing equivalents supplied, or generated by the cell from its own substrates, faster than they can be disposed of — together with their distribution across the phenotypic plane described below. They do not share a proximate condition, and the distinction is stated before the mechanisms themselves because vehicle selection, route selection and the location of each route’s failure all depend on it.
Mechanism A has a proximate condition statable in its own terms and independently of how it is reached: over-reduction of the coenzyme Q pool sustained at elevated membrane potential. The pool receives electrons from several membrane-bound dehydrogenases — Complexes I and II, and also electron-transfer flavoprotein–ubiquinone oxidoreductase, mitochondrial glycerol-3-phosphate dehydrogenase, dihydroorotate dehydrogenase and proline dehydrogenase — and discharges them through Complex III alone, which can operate only while Complex IV has oxygen available as terminal acceptor. Its reduction state is therefore the ratio between input and that outlet, and can be driven upward either by increasing input — the pharmacological route — or by closing the outlet. The latter requires no delivery at all: with oxygen below the Km of cytochrome c oxidase, Complex III stalls while Complexes I and II continue to reduce the pool using the cell’s own substrates. The asymmetry is one of topology rather than of number — many inputs, one physiological outlet — and it is not absolute. Once that outlet closes, reversal at Complexes I and II provides limited further outlets which neither regenerate the gradient nor clear the pool, and which are precisely the reactions from which Mechanism A and the accumulated succinate pool arise. What follows is therefore not that no third intervention exists, but that the two directions above are the two in which the condition can be approached, and that the mechanism which follows is indifferent to which produced it.
Mechanism B has a different proximate condition and the two should not be conflated: limitation of free NAD⁺ as an electron acceptor at the reactions that require it. That condition does not presuppose an over-reduced quinone pool at elevated potential, and in the cells where it operates it is reached without one, since the potential is not sustained. Nor does the topological argument transfer to it, since the pyridine nucleotide couple does not have the topology of the quinone pool: the terminal acceptor is oxygen in the matrix but pyruvate in the cytosol, and the two compartments are accordingly reached by different means. The two arms are set out separately below.
Mechanism A — reverse electron transport at the competent end. A reductive load imposed on a chain that is still capable of proton pumping produces two simultaneous consequences: progressive over-reduction of the coenzyme Q pool, and a protonmotive force that remains high. The second differs between the two routes in origin but not in consequence. Under donor addition the chain continues to pump throughout the pulse, so the force is raised above baseline and continuously regenerated; under acceptor subtraction pumping ceases, so the force is sustained rather than raised, maintained by hydrolytic ATP synthase operation and by the electrogenic carriers, and decaying at a rate set by proton conductance. The same permissive window is entered by both, with a different temporal profile and, as set out in Section 5.6, a different bound on duration. These are precisely the thermodynamic conditions that permit reverse electron transport (RET) at Complex I, in which electrons are driven backwards from reduced ubiquinol onto the flavin site, reducing molecular oxygen to superoxide (47, 48). RET is the principal source of reactive oxygen species in the early reperfusion phase of ischaemic injury, where succinate accumulated during ischaemia is rapidly oxidised at Complex II upon restoration of oxygen supply (47). The relevance to tumour metabolism is direct, but the origin of the succinate differs between the two routes and the distinction has consequences that are developed in Section 5.3. Under donor addition, succinate is available as an end-product of the glutaminolysis-driven mSLP pathway described in Section 2.1 (12, 13), so cells relying on that pathway enter the pulse with the RET substrate pool already elevated. Under acceptor subtraction the mSLP pathway is arrested to the degree given under Mechanism B-mit below; succinate nonetheless accumulates, as it does in ischaemia. The provenance of that pool is disputed and the framework does not depend on its resolution. Reversal of succinate dehydrogenase, driven by fumarate overflow from the purine nucleotide cycle and from partial reversal of the malate-aspartate shuttle, was proposed on the basis of flux analysis and of the protective effect of dimethyl malonate (47); stable-isotope-resolved metabolomics in hypoxic cardiomyocytes and ischaemic hearts instead attributes the accumulation principally to canonical Krebs cycle activity supported by aminotransferase anaplerosis and by glycogen-derived glycolysis (87), and a review of the earlier literature reaches the same conclusion, noting a diode-like property of the enzyme and the absence of mammalian quinones at the potentials fumarate reduction would require (88). What the mechanism proposed here requires is the pool and not its origin, and the oxidative event on restoration is established under either reading, since acute inhibition of Complex II at reperfusion is protective in both accounts (47, 87). The two routes therefore both enter reoxygenation with an elevated succinate pool. Whether the dependence on glutamine supply differs between them, as stated in Section 5.3, follows from the provenance and is settled by the isotope experiment specified in Section 6.1.
Critically, RET is not gated by a high baseline membrane potential; it requires a high potential concurrent with a reduced Q pool, sustained over time. The reductive pulse itself generates both conditions. Baseline hyperpolarisation, characteristic of epithelial carcinoma cells relative to their non-transformed counterparts (49–51), therefore acts as an offset rather than a threshold: it lowers the pulse intensity required to enter the permissive window, and predicts a gradient of efficacy rather than a categorical boundary.
What distinguishes healthy from transformed cells under this mechanism is not the amplitude reached but the duration of residence in the permissive condition. As described in Section 5.1, a healthy cell responds to a transient NADH excess by increasing respiratory flux until respiratory control intervenes; the accumulated gradient is subsequently discharged as ATP is consumed by cellular work, the chain restarts, and the reduced Q pool is cleared. A cell that cannot discharge the gradient — because gradient-discharging flux is low, as in a predominantly fermentative phenotype — remains at the ceiling, with a saturated Q pool, for the duration of the pulse. Because RET-driven superoxide production is a sustained thermodynamic condition rather than an instantaneous event, this difference in residence time translates directly into a difference in cumulative oxidative burden.
Two windows are therefore predicted, not one: during the pulse, while the permissive condition is maintained, and immediately upon its termination, when accumulated reduced substrate is rapidly re-oxidised. The second window is formally analogous to reperfusion, and its magnitude should scale with the substrate accumulated during the first. One step between the burst and cell death is named here rather than assumed. In the setting from which this mechanism is drawn, the lethal event at reperfusion is opening of the mitochondrial permeability transition pore, which requires reactive species together with matrix calcium and the return of pH toward neutrality — a condition belonging to the recovery phase rather than to the impulse, and a further reason for locating the therapeutic variable there. Mechanism B, which produces arrest without an oxidative discharge at sustained potential, is not predicted to open it.
NOTE: Throughout this work, membrane potential refers to the mitochondrial inner membrane potential (Δψm) unless the plasma membrane is named explicitly. The distinction is material: transformed cells are characteristically depolarised at the plasma membrane while being hyperpolarised at the inner mitochondrial membrane, and only the latter bears on Mechanism A. Plasma membrane depolarisation enters this framework as a terminal consequence of ATP depletion and failure of the Na⁺/K⁺-ATPase (
Section 5.1
), not as a determinant of susceptibility.
Mechanism B — limitation of free NAD⁺ at the compromised end. In cells whose respiratory chain cannot re-oxidise NADH at a sufficient rate, the same reductive load produces the opposite bioenergetic configuration: the protonmotive force does not rise appreciably, RET is not favoured, but the NADH/NAD⁺ ratio shifts sharply toward the reduced state. This mechanism has two arms, which occupy different compartments, are protected by different means, and are not reached by the same interventions. Their conflation in an earlier statement of this framework obscured a distinction on which vehicle and route selection depend.
Mechanism B-mit — the mitochondrial arm. The matrix NAD⁺ pool is re-oxidised almost exclusively at Complex I. Where chain flux ceases, whether because the chain cannot sustain it or because its outlet is closed, the matrix ratio shifts toward the reduced state within seconds. The α-ketoglutarate dehydrogenase reaction arrests for want of an electron acceptor, cutting off substrate supply to succinyl-CoA ligase and halting glutaminolysis-driven mSLP (12, 13); isocitrate dehydrogenase arrests for the same reason, and allosteric inhibition of both halts intermediary metabolism. Cytosolic lactate dehydrogenase cannot oppose this arm, because it does not have access to the compartment in which it operates. This is the arm reached by acceptor subtraction, to the degree set out in Section 5.6.1. The general form of this mechanism is already established experimentally. Inhibition of the respiratory chain kills proliferating cells principally by depriving them of electron acceptors rather than of ATP, the limiting consequence being arrest of aspartate synthesis, and supplementation with pyruvate or with α-ketobutyrate — an acceptor supplying neither carbon nor ATP — restores proliferation (78, 79). The framework proposed here differs in the means by which the acceptor is withdrawn and in the pulsed structure imposed on it, not in the principle, and the prediction that pyruvate supplementation is protective (Supplementary Material S1, prediction 4) is on this evidence already confirmed. The α-ketobutyrate control of Sullivan et al. (79) is added to the experimental panel of Section 6.1 for the reason that it isolates the acceptor function from every other property of pyruvate.
Mechanism B-cit — the cytosolic arm. Here the target is the cytosolic NAD⁺ pool and the reaction that depends on it is GAPDH, whose arrest blocks glycolysis at its principal ATP-yielding step. This arm is protected by cytosolic LDH, which regenerates NAD⁺ without mitochondrial participation, and is therefore the more difficult of the two to reach. It is reached directly by delivery of reducing equivalents to the cytosol, and by withdrawal of the cytosolic electron acceptor — inhibition of LDH, blockade of monocarboxylate transport, or accumulation of lactate under conditions in which it cannot be exported. It is not reached by oxygen withdrawal alone, for the reason given in Section 5.6.
Simultaneous arrest of both arms, together with the absence of oxidative phosphorylation, constitutes the total energy crisis described in Section 5.1, with plasma membrane depolarisation and activation of cell death pathways. Arrest of one arm alone removes a fraction of ATP supply and is not predicted to be lethal in itself.
One further consideration is required and is not supplied by the argument above. Arrest is not death. The self-reinforcing closure described in Section 5.2 concerns the substrate of lactate dehydrogenase and not the redox ratio itself, which tends to recover once glycolytic NADH production has ceased; what follows from the closure is a metabolic arrest. The arrest becomes lethal only because demand for ATP does not cease with its supply, the ion pumps continuing to consume it. Lethality under Mechanism B is therefore a question of time constants: the duration for which the cell remains arrested, against the survival time of that cell type in the absence of ATP production. Neither quantity is established here. Where the first is shorter than the second, Mechanism B predicts cytostasis rather than cytotoxicity, which is what Jin et al. (57) describe, and the absence of a permeability transition under this mechanism is the structural reason for it. The comparison is directly measurable — time to loss of plasma membrane potential and to loss of clonogenic capacity, against the duration of the imposed arrest — and is added to the endpoints of Section 6.1. A framework whose second mechanism proved cytostatic would remain valid in structure, but would require the pulse to be paired with an agent lethal to arrested cells rather than relied upon alone at the fermentative pole.
Why healthy cells escape both. A healthy cell possesses simultaneously the respiratory reserve to dispose of the imposed load (excluding Mechanism B) and the gradient-discharging flux required to discharge the accumulated gradient (limiting residence time under Mechanism A). Neither property alone confers protection; their conjunction does. This, rather than any single mitochondrial defect, is what is meant here by differential redox buffering capacity.
Two properties are therefore in play, and they are not reducible to one. The first is the capacity to re-oxidise NADH, which determines whether the load is disposed of at all. The second is the capacity to sustain membrane potential, which determines whether the RET window is entered — and which is not equivalent to the first, since a cell may sustain potential without respiring: where the chain cannot sustain it, ATP synthase may operate hydrolytically, consuming glycolytic ATP to maintain Δψ rather than discharging it. A predominantly glycolytic cell may therefore combine negligible chain flux with a high membrane potential, a combination the single axis of residual mitochondrial competence cannot represent. Phenotypes are accordingly better placed on a plane whose abscissa is the capacity to re-oxidise NADH and whose ordinate is the capacity to sustain potential from any source: the healthy cell high on both but discharging rapidly; the hyperpolarised epithelial carcinoma low on the first and high on the second, where Mechanism A is most favoured; the depolarised fermentative phenotype low on both, where Mechanism B operates; and the resistant configuration identified below high on both with rapid discharge. The axis of residual mitochondrial competence used elsewhere in this work is the projection of that plane onto its abscissa, and is retained where the distinction does not bear on the argument. One term requires precision. What determines residence in the permissive condition is the rate at which protons return to the matrix, of which flux through ATP synthase is the principal regulated component; proton leak and the electrogenic carriers, including the transhydrogenase described in Section 5.1, contribute a further and largely unregulated component that rises steeply with membrane potential. Total cellular ATP consumption is not the relevant measure. Glycolytic ATP is produced in the cytosol at the phosphoglycerate kinase and pyruvate kinase reactions, and its production consumes no gradient; where glycolytic capacity is high, rephosphorylation of cytosolic ADP competes with import through the adenine nucleotide translocase and lowers the ADP concentration presented to ATP synthase. A proliferating cell may therefore combine high absolute ATP consumption with low gradient discharge. The operative parameters are therefore the oxidative fraction of ATP production and the absolute rate of oxidative ATP turnover, neither of which is total ATP consumption, and both quantifiable by extracellular flux measurement. The same dependence has been demonstrated directly in a different setting. Increasing pyruvate oxidation lowers the NAD⁺/NADH ratio and suppresses proliferation, the proximate cause being an elevated membrane potential that constrains electron transport and hence NAD⁺ regeneration; uncoupling respiration from ATP synthesis, or increasing ATP hydrolysis, restores both the ratio and proliferation (82). That finding supports the parameter identified here, since it makes the rate of proton re-entry rather than the source of ATP the operative variable. It also bears on the objection developed below, since it establishes that uncoupling is protective in fact and not only in principle. The two are not interchangeable: the fraction identifies the source of ATP, the absolute rate the speed at which the gradient is discharged, and only the second governs residence in the permissive condition (Supplementary Material S1). A third contribution runs in the same direction and is specific to the donor-addition route. Under that route the chain continues to pump throughout the pulse, so the gradient is continuously regenerated and what determines how long the permissive condition is sustained is the total rate of proton re-entry: ATP synthase flux together with proton conductance. In a healthy cell the two are additive with the property that already confers protection, so conductance shortens residence rather than prolonging it and widens the therapeutic window on the side of safety. The same conductance in a transformed cell of low ATP synthase flux does not confer the same protection, since it bounds the potential without restoring the chain flux that clears the quinone pool — which is why the escape it affords is partial, as set out under the second open objection below. Under acceptor subtraction the contribution does not arise: there the chain does not pump, conductance dissipates a potential that is no longer regenerated, and its consequence is the bound on withdrawal duration stated in Section 5.6.
The predicted zone of resistance, and its dependence on route. The framework implies a configuration in which neither mechanism operates: cells retaining sufficient respiratory capacity to dispose of the reductive load, and with gradient-discharging flux high enough to discharge the gradient before the RET window is sustained. On the plane described above this is the region occupied by the healthy phenotype itself, which is why the configuration is resistant rather than merely less susceptible: a transformed cell that has retained both properties is protected by the same conjunction that protects healthy tissue.
This prediction is stated explicitly because it constitutes a specific way in which the model can fail. It requires, however, a restriction that an earlier statement of this framework omitted: the zone is specific to donor addition and does not transfer to acceptor subtraction. Both escapes depend on the terminal acceptor remaining available. Respiratory reserve is the capacity to pass electrons down the chain to oxygen; where oxygen is absent that reserve has no outlet, and a cell relying predominantly on oxidative phosphorylation is by construction more dependent on the acceptor, not less, since it lacks the fermentative fallback that sustains the glycolytic phenotype. The second escape is equally route-dependent. Under donor addition the chain continues to pump and the load arrives at a rate set by delivery, so ATP synthase flux can discharge the gradient as it accumulates; on restoration after acceptor subtraction, accumulated succinate is oxidised at Complex II at a rate approaching the maximum of the chain, which no physiological rate of proton re-entry matches. That this escape fails under that route is established rather than predicted: reperfusion injury occurs in cardiac and cerebral tissue, which possesses both properties to a degree no transformed cell attains (47).
Selectivity under acceptor subtraction is accordingly perfusional and spatial rather than metabolic (Section 5.6), and a metabolic category confers no resistance to a selectivity that is not metabolic. The two routes therefore have different and largely disjoint zones of resistance: donor addition is ineffective where the chain retains reserve, acceptor subtraction where perfusion restores oxygen. This constitutes an argument for their combination distinct in kind from the multiplicative argument of Section 5.5, which concerns intensity: here the combination is complementary in domain rather than in magnitude. It generates a discriminating prediction — that under donor addition alone resistance correlates positively with spare respiratory capacity, whereas under acceptor subtraction alone that same capacity is not protective and resistance correlates instead with local perfusion — which is testable with the panel and the controlled-hypoxia condition of Section 6.1.
Three qualifications bound this recovery, and one population requires separate treatment.
Cancer stem-like populations in several models — acute myeloid leukaemia, glioblastoma, breast and pancreatic carcinoma — are reported to depend on oxidative phosphorylation rather than on fermentation, retaining respiratory reserve and mitochondrial turnover competence, and non-epithelial tumours do not display the elevated membrane potential characteristic of epithelial carcinomas (50). By the argument above these are not protected from acceptor subtraction by their metabolic phenotype. They are, however, repeatedly described as possessing expanded antioxidant capacity, through elevated glutathione and constitutive NRF2 activation, and this is a genuine escape from Mechanism A: it operates downstream of the superoxide burst, buffering the discharge after it has been generated, and neither route addresses it. Combination with depletion of the glutathione pool, or with inhibition of cystine import through xCT (19), is therefore indicated specifically for this population, and is a different combination from the LDH inhibition indicated at the fermentative pole. The same population is frequently characterised by reduced MHC-I expression, which limits the immunological arm precisely where it would be most useful, and occupies both perivascular and hypoxic niches, so that its position relative to the perfusional selectivity of Section 5.6 cannot be assumed favourable. It might be supposed that repeated cycles progressively deplete this capacity. They are not predicted to. Glutathione is regenerated rather than consumed, at the expense of NADPH supplied by the pentose phosphate pathway, on a timescale of minutes — shorter than any recovery interval the framework contemplates; and under Mechanism A the nicotinamide nucleotide transhydrogenase, which is favoured rather than suppressed by the conditions the impulse creates (Section 5.1), sustains that supply in precisely the hyperpolarised phenotype in question. Repeated oxidative exposure is moreover the canonical stimulus for NRF2 activation, so cycles may induce adaptation rather than exhaust it, in the manner of ischaemic preconditioning. What does accumulate across cycles is structural: peroxidised membranes, damaged mtDNA and carbonylated proteins are removed by mitophagy and replaced by biogenesis rather than regenerated enzymatically, so cumulative damage is predicted in populations incompetent for mitochondrial turnover and not in those competent for it — the drift already described in Section 8.1(i), and the direction in which cumulative efficacy should be sought. Antioxidant capacity should therefore be measured before and after successive cycles rather than assumed to decline, since an observed rise would identify an intrinsic limit to regimens repeating an identical cycle.
Dormant and treatment-persistent cells require the opposite correction, and it follows from a distinction developed in Supplementary Material S1. What determines residence in the permissive condition is the absolute rate of proton re-entry, not the oxidative fraction of ATP production; the fraction identifies where ATP comes from, the absolute flux how fast the gradient is discharged. A quiescent cell may be oxidatively competent and yet have low absolute demand, hence low ATP synthase flux, hence prolonged rather than shortened residence. Quiescence is therefore predicted to expose such cells to Mechanism A rather than to protect them, and the resistant configuration requires competence together with high absolute oxidative turnover — a proliferating and metabolically active phenotype, not a dormant one.
Finally, the plasticity of tumour metabolism bears on the press rather than on the pulse. Since glucose restriction shifts glycolytic cells toward respiration and attenuates the hyperpolarisation on which Mechanism A depends under donor addition (50–52, Section 5.3), a sustained press may displace cells toward the resistant region of that route while leaving them fully exposed to the other. Whether this occurs, and over what timescale, is among the questions the programme of Section 6.1 is designed to settle.
The principal open objection: cytosolic LDH. In cells with high lactate dehydrogenase activity, NAD⁺ regeneration proceeds in a closed cytosolic cycle that requires neither mitochondrial participation nor export of reducing equivalents, and constitutes a quantitatively dominant route of NADH disposal (10, 52). Such cells may evade both mechanisms above, and this is acknowledged here as the principal limitation of the proposed mechanism.
It is, however, a limitation of capacity rather than of principle, and the reason is stoichiometric rather than kinetic in the first instance. Glycolysis below the triose stage is redox-neutral: it yields one NADH and one pyruvate per triose, so every pyruvate it supplies is already committed to re-oxidising the NADH it has itself produced. Lactate dehydrogenase therefore recycles endogenous reducing equivalents but confers no net capacity to dispose of an exogenous load: at steady state, with glycolytic flux J, pyruvate supplied is J while the demand on LDH is J plus the imposed load, and the deficit equals the imposed load at any value of J, including J approaching zero. What buffers an exogenous load is accordingly not the glycolytic flux but the free pyruvate pool, of the order of 10² µM and turning over within seconds, together with MCT1-mediated import from a microenvironment that is lactate-rich rather than pyruvate-rich, and the minor cytosolic reductive sinks that do not require pyruvate — principally reduction of dihydroxyacetone phosphate to glycerol-3-phosphate and of oxaloacetate to malate, whose combined capacity has not been quantified and constitutes the principal uncertainty in this estimate. The rate required to exhaust that buffer is therefore of the order of 10² µM/min rather than of the millimolar per minute implied by the glycolytic flux, and the arrest of GAPDH that follows removes the intracellular source of pyruvate, making the closure self-reinforcing (Section 5.2). On this reading the escape route is kinetically surmountable, and the slope of the impulse becomes a therapeutic variable alongside its amplitude.
Two qualifications apply. First, whether the achievable rate of delivery exceeds the rate of pyruvate supply is an empirical question that has not been tested, and the framework does not assume it. Second, the constraint is more severe in vivo than in vitro: the slope reaching a tumour cell is shaped by distribution volume, perfusion and interstitial diffusion, and in poorly perfused tumours it may be substantially flattened relative to the infusion profile. Pharmacological LDH inhibition (Section 5.5) therefore remains the more robust route to closing this escape, with kinetic saturation as a complementary and possibly sufficient alternative where delivery permits. It should also be noted that intracellular lactic acidosis, the state reached when lactate accumulates without export, reprogrammes glycolysis into a low-flux but viable configuration rather than producing immediate collapse, with LDH operating near equilibrium and coordinated inhibition of hexokinase, PFK1 and GAPDH (57). The reprogrammed low-flux state described by Jin et al. is an alternative outcome to bioenergetic collapse rather than a stage preceding it: a cell that stabilises in that configuration has not collapsed. The relevant question is therefore not whether adaptation confers resistance across cycles, but whether the impulse is sufficient to carry the cell past the threshold described in Section 5.2 rather than into quiescence — a question of intensity and slope, addressed by the pulsed-versus-continuous comparison of Section 6.1. Two considerations bear on it, and the second corrects an earlier statement of this framework. The state is phenotypic and reversible rather than heritable, so repeated cycles are not expected to select for it in the way that cytotoxic pressure selects for efflux or repair phenotypes. And the reprogrammed configuration is not one of low gradient-discharging flux. Under lactic acidosis the glycolytic contribution to ATP falls to roughly a tenth while oxidative phosphorylation supplies the remainder (86), with pyruvate cycling through export and reimport to fuel mitochondrial metabolism and with anaplerosis shifted toward lactate-derived oxaloacetate (57). A cell that stabilises in that configuration has therefore moved upward and to the right on the plane of Section 5.1.1, toward the region resistant to donor addition and fully exposed to acceptor subtraction. This is a route-discriminating prediction rather than a qualification, and it is directly testable: susceptibility to the mitochondrial clamp should fall, and susceptibility to controlled hypoxia should not, in lines pre-conditioned by intracellular lactic acidosis. The concern therefore applies to Mechanism B under the donor-addition route, where cytosolic NAD⁺ regeneration must be outpaced for the mechanism to engage at all, and not to the electrochemical route.A third qualification restricts the argument to one route. It applies only to donor addition, where a rate of delivery exists to be increased. Acceptor subtraction delivers nothing, so there is no slope to raise, and Mechanism B-cit is not reached by that route at any intensity; there the closure of this escape requires pharmacological inhibition or interruption of lactate export, as set out in Section 5.6.
The second open objection: proton leak. The mechanisms above consider disposal of the imposed load through the routes that consume NADH. A further route acts one step downstream and consumes nothing: protons re-enter the matrix independently of ATP synthase, through the basal conductance of the inner membrane and, where expressed, through inducible carriers. This lowers protonmotive force, relieves the back-pressure that slows the chain, and therefore permits Complexes III and IV to continue oxidising ubiquinol with no participation of ATP synthase. Proton leak is quantitatively substantial — estimates place it between a fifth and a half of resting respiration depending on tissue and preparation (63, 64) — and it is non-ohmic, approximately ohmic below about 150 mV and rising steeply above about 200 mV (65), which is the region the impulse is intended to occupy.
A structural consideration bounds the objection before its details are set out, and it locates rather than dissolves the escape. A conductance large enough to dissipate the load relieves the back-pressure that slows the chain, so such a cell re-oxidises NADH faster than a coupled one while sustaining little potential. It therefore occupies the region of the plane in which chain flux is high and potential is low, which is distinct from the depolarised fermentative region in which Mechanism B operates, and it escapes both mechanisms under donor addition. This constitutes a second zone of resistance alongside the one identified above, and it is established rather than predicted: uncoupling respiration from ATP synthesis restores the NAD⁺/NADH ratio and restores proliferation (82). The two zones share a structure. Both escapes require the terminal acceptor to remain available — respiratory reserve, whether realised through ATP synthase flux or through proton conductance, has no outlet once oxygen is withdrawn — so neither transfers to acceptor subtraction, and a cell of high conductance reaching reoxygenation with insufficient potential for reverse electron transport is still subject to the mitochondrial arm of Mechanism B throughout the withdrawal (Section 5.6). What follows is therefore not that high conductance confers no resistance, but that it confers resistance to one route only, which is the same complementarity in domain set out above and a further argument for combining the two. The objection remains of a different order from that posed by cytosolic LDH: LDH neutralises the load before it reaches the target compartment, whereas leak relocates the cell on the plane.
The consequence differs between the two terms of the target condition. Over-reduction of the quinone pool is not prevented: leak sustains chain flux only to the ceiling set by state 4 respiration, and load imposed above that ceiling accumulates upstream regardless. Elevation of membrane potential is constrained, the leak acting as a voltage limiter, so that term is bounded rather than proportional to the load. Since reverse electron transport requires both terms and its superoxide yield depends steeply on the second (66), leak is expected to attenuate the yield of Mechanism A at any dose. That steep dependence is itself established principally in well-coupled isolated mitochondria; uncoupling has been reported not to alter reactive species production by in situ synaptic mitochondria oxidising physiological substrates (74), which if general would make the attenuation smaller in intact tissue than the isolated-organelle data suggest.
Unlike cytosolic LDH, this route has no substrate and does not close with time, so the kinetic argument of Section 5.2 does not apply to it and duration is not a means of exhausting it. The inducible component runs in the opposite direction: uncoupling-protein-mediated conductance requires activation by superoxide and by products of lipid peroxidation such as 4-hydroxynonenal (67), and that activation requires a high membrane potential, being blunted by a fall of 10–20 mV from the resting value (68). A negative feedback therefore tightens as the impulse proceeds, and does so specifically in the condition the impulse creates. The structural response is a short and steep impulse rather than a prolonged one — one of three independent arguments converging on that parameter, the others being the cathodic pH drift and the faradaic competition of Section 8.2(j). Pharmacological inhibition exists in principle, genipin inhibiting UCP2-mediated leak (69), with UCP2 inhibition reported to sensitise carcinoma cells to therapeutic agents through increased oxidative stress (70). It should be noted that the attribution of proton conductance to UCP2 is contested, recent work describing the protein instead as a carrier of C4 metabolites (71); the basal component attributed to the adenine nucleotide translocase is not in dispute and is not pharmacologically addressable without unacceptable cost.
Whether leak abolishes the oxidative discharge or merely attenuates it is settled empirically rather than by argument. The reverse-electron-transport burst at reperfusion occurs in cardiac and cerebral tissue in which proton leak is physiologically present (47), so it is not abolished there. The reason follows from the flux ceiling: on restoration of oxygen, accumulated succinate is oxidised at Complex II at a rate approaching the maximum of the chain, whereas leak dissipates protons only at the rate corresponding to its conductance at the potential reached. The constraint is one of capacity, not of response time, since the conductance itself responds without delay. The residual yield under elevated leak is therefore a quantity to be measured rather than assumed. The analogy with reperfusion transfers directly to the acceptor-subtraction route of Section 5.6, which reproduces that sequence by construction, and only partially to donor addition, where entry into the permissive condition is more gradual. A cell combining high conductance with retained respiratory capacity and high ATP synthase flux falls into the zone of resistance already identified above.
Accessory contribution of the transplasma membrane redox system. Saturation of the extracellular environment with reducing equivalents lowers the driving force for ECTO-NOX-mediated electron transfer to extracellular acceptors (18), and connexin 43 hemichannels mediate bidirectional transmembrane fluxes of NAD⁺ whose direction depends on the transmembrane gradient (23, 53). Both contributions are expected to be quantitatively minor relative to LDH-mediated and Complex I-mediated disposal, and are proposed here as accessory rather than primary. Their relative magnitude remains to be determined experimentally.
Distinguishing the two mechanisms experimentally. The framework predicts two dissociable signatures. Mechanism A should present with elevated and sustained mitochondrial membrane potential during exposure, a reduced Q pool, and a rotenone-sensitive superoxide burst detectable at Complex I (47, 48). Mechanism B should present with a rising NADH/NAD⁺ ratio in the absence of potential elevation, modest ROS generation, and ATP depletion. Because these signatures are measurable in the same cells with existing probes, the two-mechanism structure is testable rather than merely descriptive.
Relation to existing experimental evidence. Two published findings appear at first sight to oppose the present hypothesis and require explicit comment. First, Go et al. demonstrated that clamping the cytosolic NADH/NAD⁺ redox state toward the reduced end, by imposing a high extracellular lactate-to-pyruvate ratio, protects HepG2 cells against oxidative stress-induced apoptosis, and concluded that the Warburg effect generates an anti-apoptotic extracellular environment (54). Second, the high-throughput screen of Zhao et al. identified agents that increase the NAD⁺/NADH ratio as selectively cytotoxic to cancer cells (52). Neither result contradicts the mechanism proposed here, for two distinct reasons. The clamp employed by Go et al. acts on the cytosolic compartment, whereas both mechanisms above depend on the reductive load reaching the mitochondrial compartment, which shuttle capacity may limit; a reduced cytosol does not entail an over-reduced Q pool. And the finding that oxidation is cytotoxic is consistent with, rather than contrary to, a model in which the reductive phase constitutes the loading step and the oxidative burst constitutes the lethal discharge. On this reading, the reductive impulse is not itself the cytotoxic agent; it is the condition that determines the magnitude of the subsequent oxidative event.
5.2. Press-Pulse Logic Applied to Redox State
Seyfried proposed the press-pulse strategy for metabolic cancer management, where constant metabolic “pressure” (caloric restriction, ketogenic diet) is integrated with acute “pulses” (fasting, pharmacological agents) that exploit the metabolic vulnerability of cancer cells (9). It is proposed here to extend this logic to redox state.
The reductive impulse (infusion of reducing equivalents, or imposition of a mitochondrial reductive clamp) creates an acute perturbation of the NAD⁺/NADH ratio that the healthy cell tolerates — thanks to respiratory control and endogenous antioxidant systems — and the cancer cell does not. The pause between impulses allows healthy cells to fully recover redox homeostasis, while cancer cells accumulate progressive damage with each cycle — analogously to radiation fractionation, where healthy tissue repairs damage between fractions and tumour tissue does not (35). The mechanistic basis of this differential is set out below.
Intermittency is likely superior to continuous administration for three reasons: (i) it prevents cancer cell adaptation to chronic reductive stress; (ii) it activates beneficial homeostatic mechanisms during the recovery phase (autophagy, mitochondrial biogenesis); (iii) it respects the physiological limits of the Na+/K+-ATPase pump and electrolyte homeostasis, which would not tolerate prolonged redox alteration.
A further consideration concerns the rate of delivery rather than the dose. Cytosolic NAD⁺ regeneration by LDH requires a continuous supply of pyruvate, which is limited by glycolytic flux and by MCT1-mediated import. If the reductive load is imposed faster than pyruvate can be supplied, LDH becomes substrate-limited and the cytosolic escape route closes on kinetic grounds alone, without pharmacological inhibition. The slope of the impulse is therefore predicted to be a therapeutic variable in its own right: at equal total exposure, a rapid load should exceed a gradual one, and supplementation of the medium with pyruvate should be protective. Both predictions are tested by the pulsed-versus-continuous comparison in Section 6.1, to which a pyruvate-supplemented control should be added. This also implies that collapse is threshold-dependent rather than graded. While pyruvate remains available, LDH buffers most of the imposed load and the cytosolic NADH/NAD⁺ ratio shifts only modestly; once pyruvate is exhausted, the ratio rises steeply, GAPDH arrests, and — because GAPDH lies upstream of pyruvate production — the closure becomes self-reinforcing. The existence of such a threshold is the implicit premise of press-pulse logic: without a non-linear dose–response, concentrating or diluting the same total exposure would be equivalent. Glucose restriction (Section 5.3) acts by lowering that threshold. A corollary is that slope and mechanism are not independent. Once LDH is saturated, the rate-limiting step becomes shuttle capacity: beyond that point a steeper impulse no longer increases the mitochondrial load but only the cytosolic one. In cells with limited shuttle activity, a sufficiently steep impulse should therefore shift the outcome from Mechanism A toward Mechanism B, even where residual proton-pumping capacity would have permitted reverse electron transport. Slope thus constitutes a second axis, orthogonal to mitochondrial competence, determining not only the magnitude of the effect but which mechanism is engaged. This applies to the donor-addition route; the acceptor-subtraction route is governed instead by the rate of oxygen depletion relative to perfusional resupply.
The press and the pulse are not two interventions of different kind placed side by side, but the same variable applied at two intensities and on two timescales. This is most evident in nutritional ketosis, which the framework inherits from the metabolic management of cancer as a background measure but which is, in its own right, a mitochondrial reductive clamp: the circulating β-hydroxybutyrate/acetoacetate ratio sets the mitochondrial NADH/NAD⁺ ratio through the equilibrium of β-hydroxybutyrate dehydrogenase, which is the same clamp proposed in Section 5.5 as the most tractable vehicle for reaching the mitochondrial compartment and adopted in Section 6.1 as the primary exposure condition. The dietary state is that clamp imposed continuously at low intensity; the pulse is the same clamp imposed briefly at an intensity sufficient to approach the condition of Section 5.1.1. The two are distinguished by intensity and by continuity, not by spatial extent, which is an independent property of vehicle and route and is what determines the origin of selectivity in each case. A dietary or pharmacological press is systemic and an electrochemical one regional (Section 8.2(j)); the pulse is likewise systemic under donor addition, where selectivity is metabolic, and confined to the treated volume under acceptor subtraction, where it is perfusional and spatial (Section 5.6).
The compartmental behaviour of the press is what makes the composition coherent rather than merely additive. As noted in Section 5.3, ketosis lowers circulating lactate and hence the extracellular lactate-to-pyruvate ratio, shifting the cytosolic redox state in the oxidising direction and removing the protection demonstrated by Go et al. (54), while the mitochondrial compartment is clamped in the reducing direction. The background state therefore reproduces, without administration of any vehicle, the compartmental separation on which the entire framework depends: reducing where the target lies, oxidising where the principal escape route operates.
A press constituted by exogenous reducing equivalents rather than by dietary state differs in three respects that are relevant to the framework rather than merely practical. Its intensity is set by administration rather than by the metabolic state the patient can sustain, so it is titratable and available where ketosis is not tolerated or not achieved. Its subcellular compartment of action is selectable, which the dietary clamp is not: ubiquinol acts within the inner membrane on the coenzyme Q pool itself, the variable governing Mechanism A, and being lipid-soluble is not subject to the cytosolic filtering described in Section 5.5, whereas the ketone-body clamp reaches the matrix through β-hydroxybutyrate dehydrogenase and water-soluble vehicles remain exposed to LDH. And its chemistry suits chronic administration in a way that conventional antioxidants do not, for the reasons given in Section 7.1: NADH is oxidised to a benign physiological product without radical propagation, and molecular hydrogen reacts preferentially with the hydroxyl radical while leaving species with signalling functions intact — which matters specifically in the press, where the objection to sustained antioxidant exposure is disruption of necessary redox signalling rather than acute toxicity. The corresponding limitations are those already stated: stoichiometric rather than catalytic consumption, action downstream of Complex I in the case of ubiquinol, and absence of electron donation to the chain in the case of molecular hydrogen.
The acceptor-subtraction route admits the same distinction, and the two regimes identified in Section 8.2(j) map onto it directly. The distributed configuration, in which current density and hence oxygen depletion are kept moderate and selectivity rests on perfusional asymmetry, has the properties of a press: regional rather than confined to a focal volume, of low intensity, and sustainable over repeated application. The focused configuration, producing deep local ischaemia, has the properties of a pulse. The drift predicted for each across successive cycles supports the assignment rather than complicating it: in the distributed regime mild inflammatory vasodilatation would tend to improve perfusion while making oxygen depletion harder to establish, which is a liability for a configuration intended to reach the target condition and an advantage for one intended to prepare it, since improved perfusion increases both vehicle delivery and the arrival of competent immune cells discussed in Section 7.1. Alternation between configurations across cycles, proposed in Section 8.2(j) on the grounds that they act on different variables, is on this reading an alternation between press and pulse delivered by the same means.
Three consequences follow for the framework as a whole. The press lowers the threshold the pulse must cross, in the same manner already described for glucose restriction, so that entry into the permissive condition requires less of the pulse — which relaxes the constraints that limit its duration (Section 5.1.1 and Section 8.2(j)). The press acts on a different target, addressing the chronic oxidative and inflammatory background described in Section 7.1 rather than producing selective cytotoxicity, and therefore bears on transformation as a process rather than on transformed cells as an established population. And the recovery interval belongs to the pulse rather than to the press: the reductive phase constitutes loading and the oxidative event on restoration constitutes discharge, so a continuously maintained load of pulse intensity would produce the anti-apoptotic configuration documented by Go et al. rather than the intended effect. Continuity is a property of the press and intermittency a property of the pulse, and the distinction is not a scheduling detail but the reason the two operate on different targets.
One consequence of that distinction bears on sequence, and applies specifically where the press is imposed electrochemically rather than by dietary state. A dietary press is continuous by nature and has no position within the cycle; an applied press does, and the position is not neutral. Placed before the pulse, a press acting on the thiol pool reinforces the antioxidant buffer that constitutes the residual escape from Mechanism A (Section 5.1.1), and would therefore attenuate the discharge it is meant to precede. Placed after the recovery interval, it acts on the phase in which effector function rather than oxidative discharge is the object, and on a microenvironment in which antigen has already been released. The framework accordingly predicts that a pulse–recovery–press ordering exceeds a press–pulse–recovery ordering where the press acts through that compartment, and that the interval between the applied press and the subsequent pulse must be sufficient for the thiol pool to return toward baseline. Both are testable with the glutathione endpoint specified in Section 6.1, and the two orderings are compared directly in the experimental groups proposed there.
5.3. Synergy with Glucose Restriction
Building on the two-mechanism framework described in Section 5.1.1, the efficacy of the reductive impulse is maximised — particularly in tumour cells with predominant glycolytic dependence for NAD⁺ regeneration — when they are simultaneously deprived of glucose. Under fasting or ketosis conditions, blood glucose is reduced and cancer cells are already metabolically stressed. The addition of a reducing equivalent pulse during this window creates a double attack: the missing glucose blocks glycolysis at the entry point, the NADH excess blocks it at the exit (at GAPDH, due to NAD⁺ shortage). Healthy cells, which in ketosis utilise ketone bodies as mitochondrial substrate, are less dependent on glycolysis and better tolerate the perturbation.
The reductive impulse may also perturb the metabolic coupling between glycolytic and oxidative subpopulations within heterogeneous tumours. Hypoxic cancer cells export lactate via MCT4, which is imported via MCT1 by better-oxygenated cells and used as respiratory fuel (36). Since MCT-mediated transport is governed by the substrate gradient and proton motive force rather than by extracellular redox potential (22), any effect on this shuttle would be indirect, arising from altered glycolytic flux under NAD⁺ limitation rather than from direct transport blockade. Where lactate is imported via MCT1, its intracellular oxidation to pyruvate by LDH generates additional NADH and consumes NAD⁺, which would compound the imposed reductive load in the importing subpopulation. This prediction is testable and is included among the endpoints of Section 6.1.
Two interactions with glucose restriction require explicit statement. First, the protective effect is compartment-dependent: Go et al. demonstrated that a reduced cytosolic redox state, imposed through a high extracellular lactate-to-pyruvate ratio, protects against oxidative stress-induced apoptosis (54). Since ketosis and fasting lower circulating lactate and hence the extracellular lactate-to-pyruvate ratio, glucose restriction is predicted to shift the cytosolic state in the oxidising direction, removing that protection while the reductive load is delivered to the mitochondrial compartment. Second, and in the opposite direction, the mitochondrial hyperpolarisation characteristic of glycolytic tumour cells is metabolically contingent: when such cells are shifted from aerobic glycolysis toward respiration, membrane potential returns toward values observed in non-transformed cells (49-51). Sustained glucose restriction might therefore attenuate the very condition that favours Mechanism A. Whether the two effects offset one another, and over what timescale, cannot be predicted a priori and constitutes a specific question for the experimental programme in Section 6.1.
Restriction of glutamine, the substrate of the mSLP pathway described in Section 2.1, warrants separate consideration because the framework predicts that its effect is not uniform but depends on position along the competence axis. At the compromised end, where Mechanism B operates and reverse electron transport is not favoured, glutamine restriction closes the residual mSLP-derived ATP source at no mechanistic cost, and should therefore be synergistic. At the competent end, where Mechanism A depends on succinate as the Complex II substrate driving reverse electron transport, glutamine restriction would deplete that reservoir and should therefore be antagonistic. This constitutes a specific, counterintuitive and readily falsifiable prediction, and it is restricted to one route. Under donor addition the succinate that drives reverse electron transport is supplied by the mSLP pathway, so glutamine restriction should enhance efficacy in tumours with low residual proton-pumping capacity and reduce it in tumours retaining that capacity. Under acceptor subtraction the prediction is conditional on the provenance of the succinate pool, which is disputed (Section 5.1.1). Where that pool derives from reversal of succinate dehydrogenase (47), glutamine restriction is predicted to be neutral, since the pathway supplying it is not glutamine-fed. Where it derives from canonical flux through α-ketoglutarate dehydrogenase (87, 88), glutamine restriction is predicted to be antagonistic under this route as under the other. The two branches are discriminated by the isotope-tracing experiment specified in Section 6.1, and a glutamine effect matching neither would count against the two-mechanism structure proposed here. A uniform effect in either direction across the panel, or an antagonistic effect under acceptor subtraction, would argue against the two-mechanism structure proposed here. The prediction is further complicated by the observation that intracellular lactic acidosis itself reduces glutamine dependence by promoting lactate-derived oxaloacetate formation for anaplerosis (57), so the baseline degree of glutamine reliance may vary with the metabolic state of the tumour at the time of treatment.
5.4. The Therapeutic Triad: Substrate, Structure, Environment
An integrated approach with three synergistic components is proposed (Figure 3):
Substrate (exogenous reducing equivalents): provides electrons directly usable by the respiratory chain, bypassing endogenous metabolic bottlenecks (degraded enzymes, energy deficit, redox vicious cycle). NADH is the illustrative vehicle and the one with clinical precedent; the β-hydroxybutyrate/acetoacetate clamp is the most tractable route to the mitochondrial compartment; ubiquinol operates directly in the inner mitochondrial membrane; molecular hydrogen acts as a selective reductant of the most toxic ROS.
Structure (magnesium): Mg²⁺ is an essential cofactor for over 600 enzymatic reactions, including stabilisation of the Mg-ATP complex, maintenance of iron-sulfur cluster geometry in respiratory complexes, and correct positioning of NADH at dehydrogenase active sites (37). Subclinical magnesium deficiency, which is epidemically widespread, compromises electron transfer efficiency independently of substrate availability. The dependence is quantitative rather than nominal: electron transfer between redox centres in the respiratory chain proceeds by non-adiabatic tunnelling whose rate falls exponentially with donor–acceptor distance and depends on driving force and reorganisation energy (45, 46), so the geometry of the centres is a determinant of flux and not merely of assembly.
Environment (ROS and inflammation reduction): the combination with targeted anti-inflammatory and antioxidant compounds (curcumin, EGCG, omega-3 DHA/EPA) reduces oxidative noise in the microenvironment, improving the conditions under which electron transfer occurs in healthy cells and reducing survival signals (NF-κB, HIF-1α) in cancer cells. The extracellular thiol couple belongs to this component rather than to the substrate component, since the thiol pool is a redox compartment distinct from the pyridine nucleotide and quinone pools on which the mechanisms of Section 5.1.1 operate. Its relevance is developed in Section 7.1.
Figure 3.
The therapeutic triad: substrate, structure, environment.
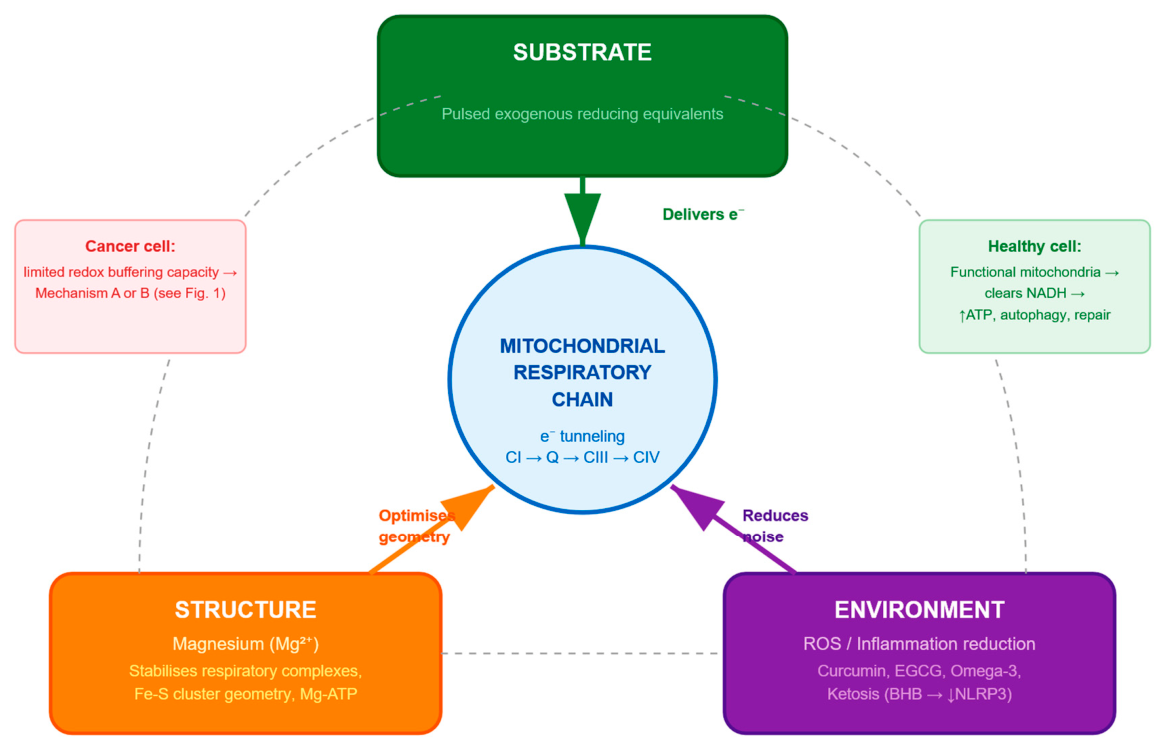
5.5. Compartment Targeting and Rational Combinations
Section 5.1.1 identifies the coenzyme Q pool as the proximate target and the mitochondrial compartment as the relevant one for the donor-addition route. This has direct consequences for vehicle selection and for combination strategy.
A thermodynamic constraint governs that selection and is stated here explicitly, since it excludes a class of approaches that might otherwise appear available. The NAD⁺/NADH couple lies near −320 mV, whereas endogenous extracellular redox couples lie far above it — the ascorbate couples at approximately +58 and +282 mV (85). No endogenous extracellular species is therefore a sufficiently strong reductant to reduce NAD⁺ across the membrane, and the trans-plasma-membrane cytochrome b561 systems (62) that relay electrons between ascorbate pools deliver them to the antioxidant pool rather than to the pyridine nucleotide pool. The vehicles proposed here are not subject to this constraint, because they do not transfer electrons across the membrane: they deliver a substrate that is oxidised intracellularly by an enzyme. The β-hydroxybutyrate/acetoacetate clamp enters as a metabolite and generates NADH in situ through β-hydroxybutyrate dehydrogenase operating at equilibrium; the lactate/pyruvate clamp does the same cytosolically through LDH. Ubiquinol acts on the quinone pool, which lies near +45 mV and is well within reach. The operative criterion for vehicle selection is therefore enzymatic oxidation of a delivered substrate, not electron transfer across a membrane.
A consequence follows for the assignment of vehicles to mechanisms, and it has not been drawn explicitly in earlier statements of this framework. Reverse electron transport oxidises ubiquinol and reduces NAD⁺, so raising the matrix NADH/NAD⁺ ratio lowers the driving force for the reaction and removes the acceptor it requires. Vehicles that load the pyridine nucleotide pools — exogenous NADH, the β-hydroxybutyrate/acetoacetate clamp, the lactate/pyruvate clamp — are accordingly vehicles for Mechanism B, and at high matrix ratios act mildly against Mechanism A rather than for it. Mechanism A is reached instead by inputs entering at or below the quinone pool: ubiquinol acting within the inner membrane, a cytosolic load routed through mitochondrial glycerol-3-phosphate dehydrogenase, and succinate at Complex II. The two mechanisms therefore share the condition of disposal being outpaced, but not the compartment loaded, and the vehicle determines which is engaged. Three consequences follow. The prediction of Section 5.2, that a sufficiently steep impulse shifts the outcome from Mechanism A toward Mechanism B in cells of limited shuttle activity, is strengthened, since it follows directly from loading the pyridine nucleotide pool and does not depend on shuttle capacity. The discriminating power of the rotenone test is increased, since rotenone inhibits reverse-electron-transport-derived superoxide while stimulating production at the flavin site in the forward direction, so the two sites respond in opposite directions. And the case for acceptor subtraction as the route of choice for Mechanism A is reinforced by an argument distinct from those already given: closing the outlet over-reduces the quinone pool while leaving the matrix NAD⁺ pool available as the acceptor that reverse electron transport requires.
A vehicle satisfying that specification exists and is endogenous. Sulfide:quinone oxidoreductase is an inner-membrane flavoenzyme that oxidises hydrogen sulfide and delivers the electrons directly to the coenzyme Q pool, intersecting the chain at the level of Complex III and bypassing Complex I entirely (90, 91). It is therefore an input of the class identified above, and the consequences of loading it have been measured rather than predicted. A sustained sulfide load limits the pool of oxidised coenzyme Q that accepts electrons from Complexes I and II, which is the proximate condition of Mechanism A as stated in Section 5.1.1; it produces a reductive shift in the NAD⁺/NADH couple whose consequence is electron-acceptor insufficiency, with deficiency of aspartate and uridine and a compensatory shift toward glutamine-dependent reductive carboxylation (90, 92), which is Mechanism B-mit reached by the aspartate-limitation route of Birsoy and Sullivan (78, 79). Both mechanisms proposed in this work are therefore obtainable with a single administered species.
What this work adds is not the identity of the donor but the manner of its imposition, and three properties of the sulfide couple bear on it. First, the species performs both directions of intervention at once: hydrogen sulfide is a substrate of the chain at low concentrations and an inhibitor of Complex IV at higher ones (90, 91, 93, 95), so donor addition and acceptor subtraction — treated as separate routes throughout Section 5.1.1 and Section 5.6 — have a single molecular realisation, in which the same species raises input to the quinone pool while closing its outlet. Second, the oxidised termini of the sulfur cycle are electrochemically accessible, so the cathode described in Section 8.2(j) can regenerate the reduced carrier in situ, converting a stoichiometrically consumed donor into one that cycles with the electrode as the electron source — the argument of Section 8.2(k), but applied to a couple whose reduced member is a genuine donor to the quinone pool, which the ascorbate couple is not for the thermodynamic reason given above. Within a volume already rendered anoxic the competition of oxygen for the applied current is removed, so the two functions of the electrode are mutually enabling here as they are in Section 8.2(l). Third, chronic rather than pulsed exposure degrades mitochondrial ultrastructure and respiratory supercomplex integrity (94), which is an independent argument for the intermittent structure proposed in Section 5.2 and against sustained delivery.
The origin of selectivity is correspondingly different and is unfavourable in one direction that must be stated. Sulfide restricts growth, and colorectal tumour tissues and cell lines counter that restriction by overexpressing the enzymes of the sulfide oxidation pathway (90); knockdown of sulfide:quinone oxidoreductase sensitises cells to the effects of sulfide (91). Disposal capacity therefore confers resistance here in the same way that cytosolic lactate dehydrogenase confers resistance under Mechanism B-cit, and the elective target of this vehicle is the lesion with low rather than high pathway expression. The resistance is specific to the vehicle and not to the framework: where expression is high, either the pathway is inhibited as a combination, or the same lesion is addressed by acceptor subtraction, whose efficacy does not depend on the target’s capacity to dispose of a delivered donor. This is the complementarity in domain of Section 5.1.1 applied to a single vehicle. Expression of the sulfide oxidation enzymes is accordingly added to the baseline characterisation of Section 6.1 and to the route-selection criteria of Table 1. Two further liabilities are noted without attenuation: elevated ubiquinol suppresses lipid peroxidation, so the same condition that produces Mechanism A attenuates one of the injuries it is intended to cause; and systemic sulfide is toxic, so this vehicle is admissible only under the spatial confinement that Section 5.6 already requires of the electrochemical route.
Vehicles differ in the compartment they reach, and the mechanism they engage differs accordingly. Intravenous NADH, being a charged and relatively large molecule, does not readily cross the plasma membrane; its direct action is therefore predominantly extracellular, and its intracellular consequences are indirect and quantitatively uncertain — the principal reason it is not proposed here as the ideal vehicle. A general constraint applies to any water-soluble vehicle: the inner mitochondrial membrane is impermeable to cytosolic NADH, whose reducing equivalents reach the matrix pyridine nucleotide pool only through the malate-aspartate shuttle. The glycerol-phosphate shuttle does not deliver them to that pool at all. Mitochondrial glycerol-3-phosphate dehydrogenase faces the intermembrane space and transfers electrons directly to the coenzyme Q pool, bypassing Complex I. The distinction is favourable to the framework rather than incidental, since that shuttle constitutes a second and cytosolically fed input to the pool which is the proximate target of Mechanism A, and it is not subject to the Complex I bottleneck. It follows that mitochondrial glycerol-3-phosphate dehydrogenase activity should be measured alongside malate-aspartate shuttle activity as a determinant of the mitochondrial load achieved, and that the two shuttles are predicted to route the same cytosolic load to different mechanisms: the first toward Mechanism B-mit, the second toward Mechanism A. Shuttle capacity is finite and frequently reduced in transformed cells, so a cytosolic reductive load does not translate proportionally into a mitochondrial one, and the fraction retained in the cytosol remains exposed to LDH-mediated disposal. Water-soluble vehicles therefore encounter the LDH escape route described in Section 5.1.1, whereas lipid-soluble vehicles acting directly within the inner membrane bypass it. Shuttle activity should therefore be measured alongside the endpoints of Section 6.1. Ubiquinol operates within the inner mitochondrial membrane and acts directly on the coenzyme Q pool, which is the variable governing Mechanism A. Molecular hydrogen diffuses freely into all compartments but does not donate electrons to the respiratory chain. A ketone-body clamp, imposed through the β-hydroxybutyrate/acetoacetate ratio, addresses the mitochondrial NADH/NAD⁺ ratio directly through the equilibrium of β-hydroxybutyrate dehydrogenase, and is the most tractable route for in vitro interrogation of the mitochondrial compartment. Any comparative evaluation of vehicles should therefore be reported against the compartment reached rather than against dose administered.
The comparison with the vehicle is stated here rather than deferred, since it is the first quantity a reader will seek. The requirement established in Section 5.1.1 is a delivered flux of the order of 10² µmol L⁻¹ min⁻¹ sustained in the target tissue. Intravenous NADH at the doses for which clinical precedent exists — of the order of tens of milligrams, hence tens of micromoles of substance — distributed even in the extracellular water alone yields bulk concentrations of a few micromolar, and does so as a bolus rather than as a sustained flux. The shortfall is of the order of three orders of magnitude before the further losses of plasma instability, restricted plasma membrane permeability, and degradation of the oxidised fraction through the salvage pathway are taken into account. NADH is therefore retained in this work as the vehicle for which a clinical route already exists and as the historical precedent for the intervention, and not as one for which the required flux is plausibly attainable. The two implementations for which the required flux is quantitatively defensible are the ketone-body clamp, whose attainable magnitude is the open parameter stated above, and acceptor subtraction, which delivers nothing and is bounded instead by charge and by perfusion.
The distance between the clamp obtainable in vivo and the clamp required is stated here as an open parameter rather than left implicit. In sustained nutritional ketosis the circulating β-hydroxybutyrate/acetoacetate ratio is of the order of 3–6:1, which through the equilibrium of β-hydroxybutyrate dehydrogenase sets a matrix NADH/NAD⁺ ratio well below that required to saturate the quinone pool. The dietary state therefore qualifies as a press and not as a pulse, consistently with Section 5.2. What remains to be established is the ratio attainable acutely by infusion of the two ketone bodies in controlled proportion, and the matrix NADH/NAD⁺ ratio it produces, measurable directly with compartment-targeted reporters. That measurement determines whether the clamp can serve as a pulse at all, and it is the first the programme of Section 6.1 should make.
The severity of this limitation differs between the mechanisms and, within Mechanism B, between its two arms. Under Mechanism B-cit the target is the cytosolic NAD⁺ pool, so LDH occupies the same compartment as the effect and can neutralise it directly; pharmacological inhibition is therefore necessary. Under Mechanism B-mit the target is the matrix pool, which LDH cannot access, so the arm is reached irrespective of LDH activity. Under Mechanism A the target is the mitochondrial coenzyme Q pool, which LDH cannot access: the enzyme acts as an upstream filter limiting how much load reaches the matrix, rather than as a means of reversing the load once delivered. A lipid-soluble vehicle acting directly on the Q pool bypasses the cytosolic compartment altogether and is therefore not subject to this limitation. Quinones conjugated to lipophilic cations accumulate in mitochondria in proportion to membrane potential (31, 32), which in this framework confers a secondary selectivity: accumulation is greatest in the hyperpolarised mitochondria of epithelial carcinomas (49–51), the phenotype in which Mechanism A is most favoured.
The vehicles and interventions discussed above are organised by two variables that are independent of one another: the compartment in which the target lies, and the direction of the intervention. Setting them out as a matrix makes explicit which combinations exist, which are unoccupied, and why.
| Addition of the donor | Subtraction of the acceptor | |
| Mitochondrial compartment target: coenzyme Q pool and matrix NAD⁺ terminal acceptor: oxygen |
β-hydroxybutyrate/acetoacetate clamp; ubiquinol acting within the inner membrane | local anoxia: cathodic oxygen consumption, vascular occlusion |
| Cytosolic compartment target: free NAD⁺ at GAPDH terminal acceptor: pyruvate |
lactate/pyruvate clamp; water-soluble vehicles, subject to LDH | LDH inhibition; monocarboxylate transport blockade; lactate accumulation without export |
Four readings follow. First, the topological argument advanced for the coenzyme Q pool — many inputs, one physiological outlet — is a property of that pool and does not generalise: the cytosolic NAD⁺ couple has several outlets, of which lactate dehydrogenase is dominant and independent of both chain and gradient, so no corresponding claim is made for the lower row. Second, the terminal acceptor is not the same species in the two rows, and the withdrawal that works in one is inoperative in the other: fermentation is by definition a mechanism for regenerating NAD⁺ without oxygen, so oxygen withdrawal does not reach the cytosolic arm and, by the Pasteur effect, accelerates it. Third, the lower left cell is expected to be protective rather than injurious on the evidence of Go et al. (54), and is retained in the programme of Section 6.1 as a compartment-discriminating control rather than as a candidate intervention. Fourth, one conflict between the cells of the matrix must be stated, since it is not apparent from their placement. β-hydroxybutyrate enters the cell through monocarboxylate transporters, principally MCT1, which are the same transporters whose blockade appears in the lower right cell as a means of reaching the cytosolic arm of Mechanism B. The two interventions are therefore mutually exclusive in the same cell at the same time, and the resolution is by arm and by phase rather than by dose. Monocarboxylate blockade belongs to the regimen directed at the cytosolic arm, in which the vehicle is not a ketone body; the ketone-body clamp belongs to the regimen directed at the mitochondrial compartment, in which lactate export is not the target. Where both arms are to be closed, either the clamp must be replaced by a vehicle independent of monocarboxylate transport — ubiquinol is the available case — or the two must be separated in time, with transport blockade following rather than accompanying the clamp. The same consideration applies to pharmacological inhibition of lactate dehydrogenase only in so far as it is combined with MCT blockade, since LDH inhibition alone does not obstruct ketone-body entry.
Glucose restriction does not appear in the matrix. It removes substrate upstream and thereby lowers the endogenous load, which alters the threshold at which the interventions above become effective without itself withdrawing an electron acceptor; it is treated in Section 5.3 as a component of the press.
Combination of donor addition with acceptor subtraction. The two routes act on opposite terms of the same balance — one increasing electron input to the coenzyme Q pool, the other closing its outlet — and are therefore expected to be multiplicative rather than additive in their effect on the reduction state of the pool. The combination also relaxes the limiting constraint of each: the admissible current density on the electrochemical side, and delivery through poor perfusion on the pharmacological side, since a given degree of Q reduction requires less of both. Sequence is predicted to matter. Vehicle distribution operates on a timescale of minutes to hours and depends on local blood flow, whereas oxygen depletion is established within seconds and itself impairs delivery; the framework therefore predicts that sequential administration, with the vehicle allowed to distribute before polarisation, exceeds simultaneous application at equal dose and charge. Two caveats apply: selectivity becomes mixed in origin, with the pharmacological component reaching tissue outside the field where spatial confinement does not protect it; and if the combined regime lowers current below the threshold for oxygen depletion, the electrochemical contribution would be absent rather than synergistic. A third consideration favours the combination in a specific subset. The inducible proton conductance described in Section 5.1.1 is activated by the products of reverse electron transport and requires an elevated membrane potential to operate (67, 68), so under donor addition it is engaged during the pulse itself, and it is engaged most strongly in the hyperpolarised phenotype retaining respiratory competence — which is also the phenotype in which Mechanism A is most favoured. Acceptor subtraction is not subject to that feedback on the same timescale, since anoxia prevents the formation of the products that activate it, as set out in Section 5.6; it remains subject to the basal component of conductance, which under that route dissipates a potential that is no longer regenerated and therefore bounds the duration of withdrawal rather than the intensity of the pulse. Where the target lesion is reachable by the electrochemical route, that route is therefore predicted to escape the dynamic component of the conductance objection in precisely the phenotype where it is strongest, at the cost of greater exposure to the basal component, while donor addition retains the advantage of systemic distribution against disease that the field does not reach.
5.6. Acceptor Subtraction as an Alternative Route to the Target Condition
The two routes identified in Section 5.1.1 are not equivalent in the demands they make. Donor addition must deliver a substrate across the plasma membrane, survive cytosolic disposal by LDH, and pass the shuttle bottleneck before reaching the compartment where the target lies. Acceptor subtraction makes none of these demands, because nothing is delivered: the reductive load is generated by the cell from its own substrates once the outlet of the coenzyme Q pool is closed.
The mechanism proceeds in four steps. The terminal acceptor is removed by lowering local oxygen tension below the Km of cytochrome c oxidase. Complex IV therefore slows, and Complex III stalls for want of a sink. Complexes I and II continue to reduce the coenzyme Q pool, since their substrates remain available, so the pool becomes over-reduced within seconds. Membrane potential is maintained in cells whose gradient-discharging flux is low, because ATP synthase discharges it slowly — the same property that under Mechanism A prolongs residence in the permissive condition (Section 5.1.1). On restoration of oxygen, accumulated succinate is rapidly re-oxidised at Complex II against a saturated Q pool, generating the conditions for reverse electron transport.
Several constraints that govern donor addition therefore do not apply. No species crosses the plasma membrane, so the thermodynamic limit stated in Section 5.5 is not encountered: NAD⁺ is not reduced from outside, and the NADH/NAD⁺ ratio rises by upstream backpressure once Complex I can no longer discharge into a saturated pool. Shuttle capacity is not rate-limiting. Cytosolic LDH intercepts nothing, because there is nothing in transit to intercept — though it remains relevant to Mechanism B, since the cytosolic NAD⁺ pool is reached only indirectly, through arrest of mitochondrial re-oxidation and of the shuttles that depend on membrane potential and Krebs-cycle substrates.
The origin of selectivity differs correspondingly. Under donor addition, selectivity is metabolic and arises from differential redox buffering capacity. Under acceptor subtraction it is perfusional and spatial: well-perfused tissue replenishes consumed oxygen from the circulation, whereas poorly perfused tumour tissue does not, and the same asymmetry operates in reverse on restoration, producing slower and less uniform reoxygenation in the tumour. The high oxygen affinity of Complex IV, which might appear to obstruct the approach by keeping respiration near-normal until oxygen falls to low micromolar levels, in fact sharpens it: the transition is steep rather than graded, so a modest difference in perfusion is amplified into a categorical difference in outcome. The framework accordingly predicts that efficacy under this route is not monotonic in perfusion. Loading requires that oxygen removal exceed resupply, which is easiest where perfusion is lowest; discharge requires rapid return of oxygen, which is fastest where perfusion is highest. Cathodic polarisation decouples the two only in part, since it consumes oxygen while leaving perfusion intact (Section 5.6.1), and the requirements remain opposed in magnitude if not in kind. The optimum therefore lies in an intermediate range rather than at either extreme, and its existence is a prediction to be demonstrated rather than an assumption. Two considerations sharpen the point. The hypoperfused core, where loading is established most easily, is already hypoxic, quiescent and HIF-adapted, and is the compartment from which minimal residual disease arises; the well-perfused periphery is where discharge is strongest and loading weakest. Perfusion imaging is proposed here as a stratification variable with a predicted optimum, not as a monotonic predictor of response, and within the treated volume the effect remains confined spatially rather than distributed by circulation.
Two limitations are intrinsic to the route and distinguish it from donor addition. It produces genuine hypoxia rather than pseudohypoxia, with the consequences set out in Section 8.1(h) operating through the canonical rather than the reductive-stress pathway. And it requires that the rate of oxygen removal exceed perfusional resupply. Supplementary Material S2 estimates that condition: sustaining depletion against maximal perfusional delivery requires an additional sink of the order of 180–620 µM O₂/min depending on local blood flow, and none at all in a hypoperfused core, where delivery already falls short of cellular consumption. The means by which such removal might be achieved, the constraint that bounds it, and the measurements that would settle the remaining uncertainty are discussed in Section 8.2(j).
Proton leak bears on this route differently. It cannot relieve over-reduction of the quinone pool, since with the outlet closed there is no chain flux for a fall in potential to restore. It continues, however, to dissipate the potential, which under oxygen withdrawal is no longer regenerated by proton pumping and is sustained only by hydrolytic ATP synthase operation and by electrogenic carriers. A cell of high conductance therefore depolarises during loading and may reach reoxygenation with insufficient potential for reverse electron transport. The duration of withdrawal is accordingly bounded on both sides: long enough to saturate the pool and accumulate succinate, short enough to retain the potential.
A second difference follows from the same separation. Under donor addition, oxygen remains available throughout the loading phase, so reverse electron transport proceeds during the pulse and the superoxide and alkenal products that activate inducible proton conductance (67, 68) are generated while the pulse is still in progress. Under acceptor subtraction the loading phase is by construction anoxic, so no such products are formed until reoxygenation — by which point the discharge is already under way. This route is therefore less exposed to the conductance feedback described in Section 5.1.1, and the argument for brevity that follows from that feedback applies to it with correspondingly less force; its own duration is bounded instead by the loss of membrane potential and by cathodic pH drift.
5.6.1. Which Mechanism Is Reached, by Which Route, and in Which Tissue
Three variables govern the outcome of acceptor subtraction and are independent of one another: availability of oxygen, supply of glucose, and clearance of lactate. Earlier statements of this framework treated them as one, and the conflation obscures a distinction between two interventions that are not equivalent. Cathodic polarisation removes the first and leaves the other two intact: it produces anoxia with perfusion preserved, so glucose continues to arrive and lactate continues to be washed out. Vascular occlusion removes all three: it produces ischaemia, in which lactate accumulates, LDH approaches equilibrium, and intracellular lactic acidosis supervenes with the coordinated inhibition of hexokinase, PFK1 and GAPDH described by Jin et al. (57). The two are therefore not alternative implementations of the same intervention; they reach different mechanisms.
The consequences follow directly. Under cathodic anoxia, Mechanism B-mit is engaged, since matrix NAD⁺ is re-oxidised almost exclusively at Complex I and cytosolic LDH has no access to that compartment. The degree of arrest is set by whatever matrix NAD⁺ is regenerated by fumarate reduction and by partial reversal of the malate-aspartate shuttle, and complete arrest is not established: canonical Krebs flux persists in ischaemic tissue and sustains substrate-level phosphorylation there, augmentation with dimethyl-α-ketoglutarate increasing both (87). The degree of arrest is accordingly among the quantities the programme of Section 6.1 is designed to measure rather than a property the route may be assumed to have.Mechanism B-cit is not reached at any intensity, since glycolysis is redox-neutral and continues unimpeded, accelerating by the Pasteur effect while substrate arrives and product is removed. Mechanism A is reached where membrane potential is sustained through the withdrawal and oxygen returns rapidly on cessation. A phenotype that is predominantly fermentative and depolarised therefore sustains arrest of mSLP alone: two of three ATP-yielding pathways are closed and the principal one remains open. Closure of the third requires inhibition of lactate dehydrogenase, blockade of monocarboxylate transport, or the anodic configuration noted in Section 8.2, and is a structural requirement of the route rather than an optional enhancement.
This assigns the electrochemical route its elective target. It is the phenotype retaining proton-pumping capacity, in a lesion that is spatially defined — not the fermentative phenotype, on which the route acts only partially. The assignment is the reverse of what a metabolic reading of the framework would suggest, and generates a falsifiable prediction: under controlled hypoxia alone, susceptibility should correlate positively with respiratory competence, whereas the addition of LDH inhibition should flatten or invert that correlation.
Two properties of the route follow from the separation of the three variables and have no counterpart in the pharmacological one. The first is that loading and discharge are decoupled: loading requires the absence of oxygen and discharge requires its rapid return, and only an intervention that consumes oxygen while leaving perfusion intact can satisfy both in the same volume. Under vascular occlusion the two requirements compete, since the vessel that was closed to produce the first must be reopened to produce the second, and reperfusion is correspondingly slower and less uniform. The second is that high-demand oxidative tissue is not exposed. The mechanism invoked here for antitumour selectivity is the same that mediates reperfusion injury in heart and brain (Section 8.1(g)), and under a systemically distributed donor those tissues receive the load; under a regionally confined withdrawal they do not. Spatial confinement, which limits the route’s reach against disseminated disease, is on this reading also its principal safety property.
A third consideration concerns vehicles that are consumed rather than recycled. Any antioxidant or reducing vehicle that donates an electron and is not regenerated is limited stoichiometrically, as set out in Section 4; a cathode that reduces the oxidised form of such a couple converts it from a consumed reagent into a carrier that cycles, with the electrode rather than the molecule as the electron source. The ascorbate/dehydroascorbate couple is the tractable case, and a qualification is required: dehydroascorbate is reduced with high capacity by erythrocytes, so regeneration is already substantial wherever blood reaches, and dehydroascorbate is labile at physiological pH with a half-life of minutes, so the cycle carries a first-order loss of carrier rather than closing on itself. The contribution is therefore expected where endogenous regeneration is least available — hypoperfused tissue, in which tumour ascorbate content is in any case reported to be lower than in matched normal tissue and to decrease with grade (59, 60). Transport to the electrode is convective rather than diffusive, since the carrier circulates, so the effective radius of this contribution is governed by local perfusion rather than by the diffusion layer that bounds oxygen depletion.

Table 1.
Criteria for route selection. Directions rather than thresholds: no preclinical data support numerical cut-offs, and the table is intended to order candidates rather than to classify them.
Table 1.
Criteria for route selection. Directions rather than thresholds: no preclinical data support numerical cut-offs, and the table is intended to order candidates rather than to classify them.
| Parameter | Measured by | Favours donor addition | Favours acceptor subtraction | Predicts resistance |
|---|---|---|---|---|
| Absolute oligomycin-sensitive respiration | extracellular flux | low |
not protective | high |
| Spare respiratory capacity | extracellular flux, maximal uncoupled rate | low | not protective; the reserve has no outlet once the acceptor is withdrawn | high |
| Membrane potential sustained during exposure | TMRM, continuous | high | high | high but rapidly discharged |
| Proton leak | extracellular flux, oligomycin-insensitive | low | low | any |
| LDH activity | enzymatic assay | low, else combine | irrelevant to B-mit; combine for B-cit | any |
| Lesion distribution | imaging | disseminated | spatially defined | any |
| Tumour perfusion | perfusion imaging | adequate, delivery required | low for loading, recoverable for discharge | any |
| Shuttle capacity | malate-aspartate activity | high | not rate-limiting | Any |
| Sulfide oxidation pathway expression (SQOR) | immunoblot, enzymatic assay | low; else combine with pathway inhibition | irrelevant | high |
The oxidative fraction of ATP production is reported as a descriptor of ATP source and is not predictive in isolation (Supplementary Material S1, Section 5).
Worked example. A spatially defined lesion, epithelial in origin, with an oxidative fraction of ATP production that is low, membrane potential sustained during exposure, low proton leak, and perfusion low enough for oxygen depletion to be established yet sufficient for reoxygenation on cessation, is a candidate for Mechanism A by the electrochemical route. The configuration indicated is monopolar, with the cathode at the lesion and the anodic half-reaction displaced outside the treated volume, so that no oxidative reaction occurs in the tissue of interest (Supplementary Material S2). The pulse is short, since the condition is established within seconds and duration is bounded by loss of membrane potential and by cathodic pH drift (Supplementary Material S2); the recovery interval, during which discharge and antigen release occur, is the principal variable and is set from the recovery kinetics of Section 6.1. Where the same lesion shows high LDH activity, inhibition of lactate dehydrogenase is added, not as an enhancement but to reach the arm that the route does not reach. Where the lesion is disseminated, the route does not apply and donor addition is indicated despite its exposure of cardiac and neural tissue. Where the phenotype is competent on both properties and discharges the gradient rapidly, donor addition is not indicated, for the reason given under the predicted zone of resistance in Section 5.1.1; acceptor subtraction remains applicable there, since that zone is specific to the route that requires the terminal acceptor to remain available, and this is the configuration in which the two routes are most clearly complementary in domain.
6. Proposed Experimental Protocol
6.1. Preclinical in Vitro Phase
The following experimental sequence is proposed, designed to test the two-mechanism framework outlined in Section 5.1.1 across the range of tumour metabolic phenotypes:
Cell line selection. Experiments should span the axis of residual mitochondrial competence described in Section 5.1.1:
- Fermentation-dominant tumour lines with documented glycolytic dependence: PC-3 and LNCaP (prostate), HeLa (cervical), MCF-7 (breast). These test Mechanism B and the LDH escape route.
- Tumour lines with elevated baseline reductive strain, as characterised by Weiss-Sadan et al. (34): KEAP1-mutant NSCLC lines (A549, H1299) and A549 treated with the KEAP1 inhibitor KI696. These test whether a mitochondrial reductive load recapitulates the vulnerability previously demonstrated with Complex I inhibition.
- A non-epithelial tumour line (haematological or osteosarcoma), which does not display the elevated membrane potential characteristic of epithelial carcinomas (50). The framework predicts attenuated Mechanism A with preserved Mechanism B — a dissociation that would provide strong internal validation if observed.
- Healthy control lines to document the therapeutic window: RWPE-1 (prostate), MCF-10A (breast), BEAS-2B (bronchial epithelium).
Exposure conditions. Cells are exposed to a defined reductive load for variable durations, followed by recovery periods in standard medium. Because the mechanisms proposed in Section 5.1.1 depend on the load reaching the mitochondrial compartment, the reductive clamp should be imposed through the β-hydroxybutyrate/acetoacetate ratio in addition to, and compared against, exogenous NADH. A cytosolic clamp through the extracellular lactate-to-pyruvate ratio should be included as a comparator, since it is expected on the basis of Go et al. (54) to be protective rather than injurious, and therefore serves as a compartment-discriminating control. Note that imposing chemical equilibrium through extracellular lactate requires concentrations in the 16–22 mM range, which measurably reduces glucose consumption; the clamp therefore perturbs energy metabolism alongside redox state, and this confound must be controlled.
Primary endpoints. The readout should capture the dissociable signatures predicted by the framework, and is divided into baseline characterisation and measurements made during and after exposure.
Baseline characterisation, prior to exposure. These parameters are measured in each line before treatment and correlated with subsequent susceptibility; together they constitute the candidate predictive biomarker for translational application.
- Oxidative fraction of ATP production, and the absolute rate of oligomycin-sensitive respiration, reported separately. The two are not interchangeable: the fraction identifies the source of ATP, the absolute rate the speed at which the gradient is discharged, and only the second governs residence in the permissive condition (Supplementary Material S1).
- Spare respiratory capacity and basal oxygen consumption (Seahorse extracellular flux analysis).
- Proton leak, obtained from the same trace: the oligomycin-insensitive oxygen consumption remaining after subtraction of the non-mitochondrial rate defined by rotenone and antimycin A.
- LDH activity, as the predicted determinant of escape from Mechanism B-cit and, under donor addition, of the load reaching the matrix.
- Malate-aspartate shuttle activity, as the determinant of how much of a cytosolic load reaches the mitochondrial compartment (Section 5.5).
- Basal NADH/NAD⁺ ratio, cytosolic and mitochondrial.
During and after exposure.
- Cell viability: MTT assay, trypan blue exclusion, clonogenic survival.
- Cytosolic and mitochondrial NADH/NAD⁺ ratios: genetically encoded reporters (SoNar, Peredox) with compartment-targeted variants, to establish whether the load reaches the mitochondrial compartment.
- Mitochondrial membrane potential measured continuously during exposure (TMRM), not only at baseline. The framework predicts that the duration of residence at elevated potential, rather than the baseline value, discriminates susceptible from resistant cells.
- Mitochondrial superoxide in the minutes immediately following washout (MitoSOX), with and without rotenone, to test whether a rotenone-sensitive burst occurs on restoration of basal conditions, as predicted by the analogy with reperfusion injury (47).
- ATP levels, with separate assessment of glycolytic and OxPhos contributions.
- Intracellular and extracellular lactate, to test the prediction in Section 5.3 regarding lactate-importing subpopulations.
- Oxygen tension measured locally during exposure, as the variable determining whether the acceptor-subtraction route reaches the threshold at which Complex IV becomes rate-limiting.
- Provenance of the succinate pool accumulated during withdrawal, by ¹³C tracing from aspartate, glutamine and glucose, with a dimethyl-malonate arm. This discriminates reversal of succinate dehydrogenase from canonical Krebs flux (47, 87, 88), and the glutamine prediction of Section 5.3 follows from the outcome.
- Matrix NAD⁺ and the flux through α-ketoglutarate dehydrogenase during withdrawal, to establish the degree rather than the fact of the arrest described in Section 5.6.1.
- Proton leak, remeasured after each cycle rather than at baseline alone, to test the drift described in Section 8.1(i). No additional experiment is required.
- Total and oxidised glutathione, and NRF2 target gene expression, measured after each cycle rather than at baseline alone, to establish whether antioxidant capacity declines, recovers, or rises across the series.
Experimental groups. Each condition is run in matched pulsed and continuous regimens at equal total exposure, since the comparison between the two is the direct test of press-pulse logic:
- Mitochondrial reductive clamp (β-hydroxybutyrate/acetoacetate).
- Exogenous NADH, retained as a negative control discriminating both compartment and mechanism rather than as a candidate vehicle: the framework predicts that it is markedly less effective than the mitochondrial clamp at equal nominal reductive load, and that neither produces the Mechanism A signature, since both load the pyridine nucleotide pools rather than the quinone pool (Section 5.5). Comparable efficacy would indicate that the compartmental argument does not hold; appearance of a rotenone-sensitive burst under either clamp would indicate that the assignment of vehicles to mechanisms does not hold.
- Cytosolic clamp (lactate/pyruvate), as compartment-discriminating comparator.
- LDH inhibition alone.
- Complex I inhibition alone (IACS-010759 or rotenone), as a direct test of the Weiss-Sadan mechanism.
- Reductive clamp combined with LDH inhibition.
- Reductive clamp in glucose-free medium, testing the interaction described in Section 5.3.
- Untreated control.
- Reductive clamp with pyruvate supplementation, and in parallel with α-ketobutyrate supplementation, as a test of the kinetic substrate-limitation mechanism described in Section 5.2. The second isolates the electron-acceptor function from the carbon and energetic contributions of pyruvate (79).
- Reductive clamp in glutamine-free medium, testing the opposite-direction prediction described in Section 5.3.
- Acceptor subtraction by controlled hypoxia, as an in vitro surrogate for the acceptor-subtraction route of Section 5.6: defined reduction of medium oxygen tension for the pulse duration, followed by rapid reoxygenation. The framework predicts that this produces the same coenzyme Q over-reduction as donor addition, without any species crossing the plasma membrane, and that the rotenone-sensitive ROS burst on reoxygenation is comparable in magnitude.
- Combined donor addition and controlled hypoxia, applied sequentially, testing the multiplicative interaction predicted in Section 5.5. The framework predicts that sequential application exceeds simultaneous application, and that both exceed either route alone.
- Reductive clamp combined with inhibition of inducible proton conductance (genipin), as the counterpart to the LDH-inhibition condition, testing whether limiting that conductance restores the Mechanism A signature in lines where it is otherwise attenuated.
- Acceptor subtraction by controlled hypoxia combined with LDH inhibition, as the test of whether closure of the cytosolic arm converts partial to complete arrest at the fermentative pole.
- Reductive clamp, and controlled hypoxia, each combined with glutathione depletion or xCT inhibition, as the test of whether expanded antioxidant capacity constitutes the residual escape from Mechanism A in lines with constitutive NRF2 activation.
- Thiol-directed press applied before the pulse, compared with the same press applied after the recovery interval, at equal total exposure, with characterisation of the immune infiltrate and of the rotenone-sensitive burst as endpoints. The framework predicts that the second ordering preserves the discharge while the first attenuates it.
- Reductive clamp and controlled hypoxia applied to lines expressing LbNOX or mitochondrially targeted LbNOX (80), as the compartment-resolved rescue experiment. These genetically encoded water-forming NADH oxidases raise the NAD⁺/NADH ratio in the compartment to which they are directed, so they act in the direction opposite to the imposed load and permit the compartmental claim to be tested by rescue rather than by comparison of clamps. The framework predicts that mitochondrially targeted expression rescues the mitochondrial arm and not the cytosolic one, and that cytosolic expression rescues the converse; failure of either dissociation would invalidate the compartmental argument more directly than any clamp comparator. The NADPH-specific variant (81) resolves whether the residual escape from Mechanism A operates through the glutathione system.
- Lines pre-conditioned by intracellular lactic acidosis (20 mM lactate, pH 6.7), then exposed to the mitochondrial clamp and to controlled hypoxia in parallel. The framework predicts that pre-conditioning confers resistance to the first and not to the second.
- Ubiquinol, and a cytosolic load imposed under conditions favouring the glycerol-phosphate shuttle, as the Mechanism A vehicle arm. The framework predicts a rotenone-sensitive burst here and not under the pyridine nucleotide clamps of groups 1 to 3, at equal nominal reductive load.
- A sulfide donor delivered to the coenzyme Q pool, in matched pulsed and continuous regimens at equal total exposure, as the Mechanism A vehicle arm. The framework predicts a rotenone-sensitive burst on washout under this vehicle and not under the pyridine nucleotide clamps of groups 1 to 3, and that the pulsed regimen exceeds the continuous one — the direct test of the press-pulse claim with a vehicle whose steady-state effects are already characterised (90-92).
- The same, combined with knockdown or inhibition of sulfide:quinone oxidoreductase, as the test of whether pathway expression governs resistance in the manner predicted.
- Concentration series spanning the transition from stimulation to inhibition of respiration, to establish whether a single species can be titrated across both directions of intervention in the same cell.
Predictions and falsification criteria. The framework predicts, for donor addition: that susceptibility correlates with low spare respiratory capacity, a low absolute rate of oligomycin-sensitive respiration, low LDH activity and sustained elevation of membrane potential during exposure, independently of glycolytic or oxidative classification. For acceptor subtraction it predicts the opposite dependence on the first of these: spare respiratory capacity should not be protective, since the reserve it measures has no outlet once the terminal acceptor is withdrawn, and susceptibility should instead track the rate at which oxygen is restored on cessation. Divergence of the two rankings across the same panel is the direct test of the route-specificity of the resistant zone set out in Section 5.1.1; convergence would indicate that the two routes are not distinct in the manner claimed. The framework predicts further: that the ROS burst is rotenone-sensitive and maximal immediately after washout; that pulsed regimens exceed continuous regimens at equal total exposure; that the cytosolic clamp is protective while the mitochondrial clamp is injurious; and that the rotenone-sensitive burst on washout correlates inversely with baseline proton leak, lines of high leak displaying the Mechanism B signature — a rising NADH/NAD⁺ ratio without potential elevation — at a steeper imposed slope rather than displaying resistance. The framework further predicts that proton conductance is itself modified by repeated cycles, rising in lines incompetent for mitochondrial turnover and falling in those competent for it; its observation would identify an intrinsic limit to regimens that repeat an identical cycle, and would be grounds for the sequenced alternative described in Section 8.1(i). Failure of the compartmental prediction in particular would indicate that compartmental separation does not operate as proposed, and would invalidate the framework as stated. The framework further predicts that donor addition and acceptor subtraction, applied separately to lines retaining proton-pumping capacity, converge on the same proximate condition — an over-reduced coenzyme Q pool at elevated membrane potential — and produce the same Mechanism A signature: a rotenone-sensitive superoxide burst on restoration, of comparable magnitude at comparable pool reduction. The prediction is restricted to that signature. The two routes are not predicted to be indistinguishable in other respects: the temporal profile of membrane potential differs, being raised and continuously regenerated under donor addition and sustained but decaying under acceptor subtraction; mitochondrial substrate-level phosphorylation is arrested by acceptor subtraction and not by donor addition; and the cytosolic arm of Mechanism B is reached only by the first. Divergence of the Mechanism A signature itself would indicate that the two routes are not equivalent at the level claimed and would require the framework to be restated.
6.2. Modalities for Reducing Equivalent Delivery
The central principle — pulsed perturbation of intracellular redox state through exogenous reducing equivalents — can be achieved through various modalities, each with specific advantages and limitations:
Exogenous NADH: is the native substrate of the respiratory chain and the most direct vehicle. It is administered parenterally in published clinical work in Parkinson’s disease (7, 89), and by infusion in an oncological setting at the Hyperthermia Centre Hannover (8), though no peer-reviewed efficacy or pharmacokinetic data exist for the latter application. Advantages: an established route of administration, direct enzymatic recognition. Limitations: molecular instability, limited membrane permeability. Delivery in liposomes or nanoparticles could improve intracellular bioavailability and potentially enable tumour targeting through the EPR (enhanced permeability and retention) effect.
Ubiquinol (reduced CoQ10): operates directly in the inner mitochondrial membrane as an electron carrier between complexes I-II and complex III. Advantages: direct access to the site of action, lipid solubility, good safety profile. Limitations: does not bypass blockade at the complex I level, acts downstream in the electron pathway.
Molecular hydrogen (H₂): a selective reductant that preferentially reacts with the hydroxyl radical (OH•) without neutralising reactive species with signaling functions (O₂•⁻, H₂O₂). Advantages: unique selectivity, small molecular dimensions that allow diffusion into every cellular compartment, clinical trials underway in Japan. Limitations: does not supply electrons to the respiratory chain, acts primarily as a selective scavenger.
Other modalities: the principle proposed here — pulsed perturbation of intracellular redox state — is not bound to a specific molecular vehicle. Any technique, molecule, or procedure capable of acutely increasing the intracellular load of reducing equivalents could be evaluated within this framework, with particular interest in systems designed to deliver a defined reductive load to the mitochondrial compartment. The future development of catalytic redox vehicles — capable of cycling between oxidation states without being consumed — would represent a significant advancement over stoichiometric vehicles such as NADH. Each of these modalities would merit independent experimental evaluation within the press-pulse framework proposed here. NADH is suggested as the first vehicle to be tested, on grounds of safety of administration, endogenous status and existing clinical precedent, and not on grounds of mechanistic optimality. As set out in Section 1, Section 5.5 and Section 8.1(b), limited membrane permeability, plasma instability, stoichiometric consumption and the fate of the fraction oxidised to NAD⁺ all argue against it as the vehicle of choice; it is retained here because it is the vehicle for which a clinical route already exists, and because a framework that cannot be tested with an available agent cannot be tested at all.
6.3. Illustrative Press and Pulse Parameters (Not a Validated Protocol)
The parameters below are presented solely to indicate the order of magnitude of the variables that a future Phase I design would need to establish. No preclinical data supporting any of them exist at the time of writing, and the mechanism proposed in Section 5.1.1 is shared with reperfusion injury in cardiac and neural tissue (Section 8.1). These figures must not be applied in any clinical or quasi-clinical setting, and are not a dosing recommendation. The metabolic combination with fasting, previously suggested, is omitted here: the dose-limiting toxicities reported for Complex I inhibition in Phase I were lactic acidosis and neuropathy (56), and concurrent substrate restriction would be expected to compound rather than mitigate the first of these.
- Press: a continuous background of reduced intensity, operating on a timescale of hours to days, and either regional or systemic depending on the vehicle and route employed, whose purpose is to lower the threshold at which the pulse becomes effective and to act on the chronic oxidative and inflammatory background rather than to produce cytotoxicity. The systemic form shares its requirements with the preventive application of Section 7.4, and the considerations on route given there apply to it. None of the considerations that constrain pulse duration applies at this intensity, the target condition of Section 5.1.1 not being approached.
- Pulse duration: minutes for the acceptor-subtraction route, where the condition is established within seconds; for donor addition the achievable duration is bounded below by vehicle distribution, which operates on a timescale of minutes to hours (Section 5.5), so the pulse is defined by the interval of residence in the permissive condition rather than by the infusion itself.
- Inter-pulse recovery interval: the principal therapeutic variable, to be determined from the recovery kinetics measured in Section 6.1 rather than assumed.
- Mandatory monitoring in any future trial: plasma NAD⁺/NADH ratio, blood lactate, glucose, ketones, continuous ECG, electrolytes, inflammatory markers, complete blood count
- Cardiac and neurological monitoring beyond standard requirements, given the mechanism described in Section 8.1(g)
6.4. Safety Criteria
NADH is an endogenous molecule with a favourable safety profile in available clinical experience (7, 8). However, the pulse protocol with doses potentially higher than those used for anti-aging requires specific attention to:
- • Cardiac risk: acute alterations of the NAD⁺/NADH ratio may affect cardiomyocyte membrane potential. Continuous ECG monitoring during infusion is mandatory.
- • Metabolic risk: an excessive infusion rate could cause paradoxical lactic acidosis or excessively activate respiratory control, reducing ATP production in healthy cells. Gradual dose titration is recommended.
- • Electrolyte risk: reductive stress could transiently affect the Na+/K+-ATPase pump. Monitoring of electrolytes before, during, and after infusion is essential.
7. Anti-Cancer and Anti-Aging Convergence
7.1. Shared Mechanisms
Cyclic reductive impulses activate pathways that are simultaneously anti-tumoral and anti-aging:
Autophagy and mitophagy: the transient metabolic stress induced by the reductive impulse, especially in combination with fasting, activates autophagy — the process of recycling damaged cellular components (38). Mitophagy, in particular, removes dysfunctional mitochondria and replaces them with new mitochondria through PGC-1α-mediated mitochondrial biogenesis. This process is fundamental both for eliminating potentially pro-tumoral mitochondria and for rejuvenating the cellular mitochondrial pool (39).
AMPK/mTOR axis: the metabolic impulse activates AMPK (energy scarcity sensor) and inhibits mTOR (abundance sensor). This switch activates cellular repair and recycling programs and suppresses proliferation — beneficial both in anti-tumour and anti-aging contexts (40).
Elimination of senescent cells: senescent cells — which have ceased dividing but secrete pro-inflammatory cytokines (SASP, senescence-associated secretory phenotype) — are drivers of both aging and tumorigenesis (41). Cyclic metabolic impulses promote the selective elimination of these cells through autophagy and immune activation.
Reduction of chronic inflammation (inflammaging): beta-hydroxybutyrate, the principal ketone body produced during fasting and ketosis, directly inhibits the NLRP3 inflammasome (42), reducing the chronic low-grade inflammation that serves as a substrate for both aging and tumorigenesis.
Direct reduction of chronic oxidative burden through non-radical-generating vehicles: Beyond the hormetic activation of repair programs, the reductive impulse exerts a direct and immediate antioxidant effect through cathodic reduction of the extracellular thiol couple, which is a concrete mechanism rather than a general antioxidant claim and belongs specifically to the electrochemical implementation of the press. Chronic low-grade oxidative stress — generated continuously by mitochondrial electron leak, NADPH oxidases, inflammatory infiltrates, and age-related accumulation of oxidised macromolecules — is recognised as a central driver of aging across multiple hallmark processes: mitochondrial dysfunction via cardiolipin peroxidation and mtDNA damage, cellular senescence via oxidative DNA lesions, inflammaging via oxidised-molecule-driven NLRP3 activation, and loss of proteostasis via protein carbonylation. A pulsed reductive impulse transiently attenuates this oxidative burden, providing a window during which damaged components can be repaired or cleared without the competing pressure of ongoing oxidative insult.
This mechanism is qualitatively different from classical exogenous antioxidant strategies (vitamin C, vitamin E, glutathione), which fail in chronic administration for two distinct reasons elaborated in Section 4.2: (i) they disrupt physiologically necessary redox signaling when maintained at elevated levels, and (ii) they themselves become radical species upon electron donation, with stoichiometric consumption and — in the case of vitamin C in iron-rich environments such as the tumour microenvironment — active propagation of the Fenton cycle to generate hydroxyl radicals. NADH, by contrast, is oxidised to NAD⁺, a benign physiological product that is rapidly metabolised through established pathways without radical propagation. The vehicle-level difference therefore compounds the temporal-level difference: a pulsed intervention with a non-radical-generating vehicle operates on fundamentally different kinetic and chemical principles than chronic supplementation with radical-generating antioxidants. This distinction extends naturally to the future development of catalytic redox vehicles capable of cycling between oxidation states without stoichiometric consumption (Section 6.2), which would represent a further advancement by combining pulsed delivery, non-radical product chemistry, and catalytic persistence in a single framework.
It is important to distinguish the anti-aging mechanism proposed here from the prevailing NAD⁺ supplementation paradigm (NMN, NR, intravenous NAD⁺). While NAD⁺ supplementation aims to directly restore the declining intracellular NAD⁺ pool, the pulsed reductive approach operates through a fundamentally different mechanism: hormesis-driven cellular renewal. The transient reductive stress induced by the impulse — regardless of the specific reducing vehicle employed — activates compensatory homeostatic programs during the recovery phase, including PGC-1α-mediated mitochondrial biogenesis, AMPK-driven autophagy, and upregulation of the NAD⁺ salvage pathway via NAMPT. The net effect is not a passive replenishment of NAD⁺ from an external source, but an active regeneration of the cellular machinery responsible for NAD⁺ homeostasis — analogous to the well-documented benefits of intermittent fasting and exercise, which transiently stress cellular metabolism to produce lasting adaptive improvements. It should be noted that the present framework does not claim an additional benefit from the fraction of exogenous NADH oxidised to NAD⁺ in plasma. Such a claim would stand in direct contradiction to the concern raised in Section 2.2, and the position taken here is the more conservative one: any systemic elevation of circulating NAD⁺ is treated as a potential liability rather than as a secondary benefit. Since NADH is in any case not proposed as the optimal vehicle, nothing of substance is lost by this concession. The anti-aging mechanism proposed here rests entirely on hormesis-driven cellular renewal — PGC-1α-mediated mitochondrial biogenesis, AMPK-driven autophagy, and upregulation of the NAD⁺ salvage pathway during the recovery phase — and not on exogenous replenishment of the NAD⁺ pool.
Two immunological consequences are proposed here and they have different requirements, which an earlier statement of this framework did not separate. The immunogenic arm requires cell death of the oxidative kind, with release of calreticulin, HMGB1 and ATP, dendritic maturation and presentation in the draining node; it therefore requires Mechanism A, and does not arise where the load produces bioenergetic arrest without an oxidative discharge. The environmental arm requires no cell death at all: it consists in transient attenuation of the oxidative and metabolic barrier that suppresses effector function, and operates wherever the perturbation is applied. The distinction matters because the two arms apply to different phenotypes. At the competent pole both are available; at the fermentative pole, where Mechanism A is not engaged, only the second is, and the framework there proposes conditioning of the microenvironment rather than cytotoxicity — an objective for which the low-intensity regime described in Section 8.2(j) may be more appropriate than the intensity required to reach the target condition, and which is naturally combined with an agent supplying the antigen that conditioning alone does not provide.
The asymmetry on which the environmental arm rests should be stated explicitly, since it is what makes attenuation of reactive species therapeutically asymmetric rather than merely general. Reactive oxygen species in the tumour microenvironment impair infiltrating lymphocytes while being tolerated by transformed cells, which possess upregulated antioxidant systems and employ these species as proliferative signals (16, 17). Their transient attenuation therefore removes little from the tumour and returns much to the lymphocyte.
A second contribution to the environmental arm is available in the press and not in the pulse. Cystine is the dominant extracellular thiol and its reduction product is rate-limiting for glutathione synthesis; T lymphocytes depend, during activation, on cysteine supplied by antigen-presenting cells (75), so this is a documented bottleneck on effector function rather than a general antioxidant effect (76, 77). A reductive perturbation acting on this couple during the recovery interval therefore acts on that bottleneck specifically, and its anti-inflammatory consequence follows by a defined route — restoration of the glutathione precursor supply to infiltrating lymphocytes — rather than by unspecified scavenging.
The electrochemical implementation gives that perturbation a mechanism, and the mechanism satisfies the criterion of Section 5.5 without qualification: the cathode reduces cystine in the extracellular space, and its product cysteine enters cells as a transported reduced substrate, so that no electron crosses the plasma membrane and the thermodynamic constraint of that section is not encountered. The route differs from supplying cystine itself. Cystine is imported through xCT, which is overexpressed in transformed cells and is the locus of the depletion imposed by myeloid-derived suppressor cells (76); cysteine is imported through neutral amino acid transporters available to lymphocytes. Cathodic reduction therefore bypasses the contested transporter rather than competing at it, and delivers the rate-limiting precursor to the population in which it is limiting (75, 77).
The faradaic economics of that reduction differ between the two regimes of Section 8.2(j), and the difference is one of spatial scale rather than of oxygen availability in the tissue. Reduction of dissolved oxygen at a cathode is limited by transport to the surface, so it draws a current ceiling set by the local oxygen concentration and by the thickness of the diffusion layer, rather than a fixed share of whatever current is applied. What determines whether other solutes are reduced is accordingly the excess of applied current over that ceiling, and the ceiling is a property of the electrode surface and not of the tissue. A press configuration of large electrode area and low current density, operated at or slightly above the local limiting current, therefore depletes oxygen within a diffusion layer of tens of micrometres and reduces cystine there, while the surrounding tissue remains normoxic and no volume falls below the functional threshold of Complex IV. Perfusion, which is intact throughout, carries the product away from the shell in which it is generated and distributes it regionally. This is the sense in which the contribution belongs to the press: it requires depletion at the surface and not in the tissue, and it establishes no condition of Section 5.1.1 anywhere.
The pulse differs in that the depletion front leaves the diffusion layer and propagates into the treated volume, which is the condition Mechanism A requires. From that point the same thiol reduction proceeds within the tissue in which the discharge must occur, and reinforces the antioxidant buffer that constitutes the residual escape from that mechanism. This is the third argument for terminating the impulse at depletion given in Section 8.2(j), and it should be read precisely: the impulse is terminated not when thiol reduction begins, since it begins at the surface as soon as the limiting current is exceeded, but when the volume in which it proceeds becomes the volume in which the discharge is intended. The two regimes therefore generate the same product at different scales and with opposite intent — deliberately and within a thin shell in the press, incidentally and throughout the treated volume in the pulse, where it is to be avoided.
Two constraints qualify the press configuration and neither is removed by the argument above. Direct electrochemical reduction of a disulfide is kinetically sluggish on most electrode materials and may proceed with poor yield at any potential compatible with tissue, independently of competition from oxygen; the faradaic yield for this reaction on a specified material is therefore a measurement rather than an assumption, and is obtained from the partition determined in Supplementary Material S2, Section 9(6). And current in excess of the oxygen-limiting value reaches water as well as cystine, so the press is not exempt from the alkalinisation constraint: what keeps its pH excursion small is the distribution of that charge over a large electrode area and a large tissue volume, with perfusion and bicarbonate resupply intact, and not the smallness of the charge itself.
Two consequences follow. The sign of this contribution is opposite to that of the glutathione depletion proposed in Section 5.1.1 against the residual escape from Mechanism A, and the two are reconciled by phase rather than by dose: the thiol pool is reinforced during recovery, when effector function is the object, and not during the pulse, when the oxidative discharge is. And the interval required for the pool to return toward baseline before a subsequent pulse is a scheduling variable rather than a detail, measurable with the glutathione endpoint of Section 6.1 and compared directly in experimental group 16.
A liability specific to this route must be stated alongside it, since it is the chemistry identified for ascorbate in Section 4.2. Cysteine is a reductant of transition metals and autoxidises by a metal-catalysed route, generating superoxide and hydrogen peroxide, so the objection applies in kind. Two differences bound it. The couple is a two-electron thiol–disulfide couple and a less efficient one-electron reductant of ferric iron than ascorbate. And the roles differ structurally: ascorbate is proposed in Section 8.2(k) as a carrier that must persist extracellularly in order to cycle, so its pro-oxidant chemistry is sustained by design, whereas cysteine is a consumed precursor whose extracellular residence is a transit terminated by uptake and by incorporation into glutathione. The liability accordingly scales with extracellular residence time against uptake rate, and is bounded rather than structural. What remains is the fraction generated within a depleted volume and not yet taken up when oxygen returns, which autoxidises at reoxygenation; its magnitude is set by the same competition of time constants and is measurable, by extracellular cysteine, hydrogen peroxide and labile iron in the treated volume across the press interval and across the recovery phase. A net oxidising result would confine this contribution to tissue of low labile iron content.
Transient immune unmasking of tumour cells (hypothesis). Cancer cells exploit chronic oxidative inflammation in the tumour microenvironment to create an immunosuppressive niche: elevated ROS inactivate infiltrating T lymphocytes and polarise tumour-associated macrophages toward the pro-tumoral M2 phenotype (17). The following is advanced as a predicted consequence requiring experimental verification, not as an established mechanism. An objection must be stated first: T lymphocyte activation requires mitochondrial reactive oxygen species for TCR signalling, so attenuation of ROS would be expected to suppress rather than liberate the immune response. The proposal advanced here depends on temporal dissociation — attenuation during the pulse, immune re-entry during recovery — and therefore requires that the kinetics of redox recovery and of immune functional restoration overlap. This is not established: redox recovery occurs over minutes to hours, whereas reversal of T cell exhaustion is a transcriptional and epigenetic process operating over days. A partial resolution follows from the selectivity principle itself. The objection applies to lymphocytes already infiltrating the tumour, which constitute the exhausted population; circulating lymphocytes, possessing competent mitochondria, tolerate the perturbation for the same reason healthy cells do, and are recruited by chemokine signalling on a timescale of hours. On this reading the framework does not require restoration of exhausted cells but recruitment of competent ones, together with immunogenic cell death — release of damage-associated molecular patterns from dying tumour cells, dendritic cell maturation and antigen presentation in the draining lymph node. The proposition should be regarded as open, and is testable through characterisation of the immune infiltrate at defined intervals across the pulse-recovery cycle. With that qualification, the reductive impulse, by transiently attenuating extracellular ROS — either through direct scavenging by membrane-permeable reducing agents or through saturation of membrane-associated ECTO-NOX systems that suppresses ROS generation — and reducing the oxidative inflammatory signals in the tumour stroma, may temporarily disrupt this immunosuppressive shield. During the recovery phase following the impulse, the immune system — functionally restored by the transient reduction of oxidative stress — could re-enter a microenvironment where the tumour’s immunoevasion mechanisms have not yet been fully re-established, facilitating immune recognition and attack. This potential immunometabolic synergy between reductive impulses and anti-tumour immunity warrants specific experimental investigation.
This immunometabolic mechanism acquires additional significance in light of the recent discovery that cancer cells can hijack mitochondria from infiltrating CD8+ T cells and natural killer (NK) cells via intercellular nanotubes (43). This mitochondrial theft simultaneously strengthens the cancer cell — by providing functional mitochondria for ROS scavenging, ATP production, and treatment resistance — and weakens the immune cell, accelerating its functional exhaustion. The reductive impulse may disrupt this parasitic interaction at multiple levels: (i) by depleting the cancer cell’s ATP, it impairs the energy-dependent formation and maintenance of intercellular nanotubes; (ii) by neutralising extracellular ROS and reducing microenvironmental acidosis, it attenuates the signals that drive T cell exhaustion and PD-1 overexpression, thereby preserving immune cell metabolic competence; (iii) by transiently disrupting the immunosuppressive polarisation of tumour-associated macrophages (TAM) from the pro-tumoral M2 phenotype toward the anti-tumoral M1 phenotype (17), it removes a key source of T cell suppression. The net result is a transient inversion of the immunometabolic balance in the tumour microenvironment: during the recovery phase following the impulse, metabolically compromised cancer cells face a functionally restored immune system in a microenvironment where the immunosuppressive shield has not yet been re-established.
An important consideration is whether the partial oxidation of exogenous NADH to NAD⁺ in the plasma might exacerbate the immunosuppressive NAD⁺ depletion imposed by tumour-overexpressed CD38 on infiltrating T lymphocytes. Three observations suggest this is not the case. First, the reductive impulse does not worsen the pre-existing immunosuppressive state: CD38-mediated NAD⁺ depletion in the tumour microenvironment is already maximal at baseline, and the impulse does not upregulate CD38 activity. Second, the immune-restorative mechanism of the reductive impulse operates primarily through the neutralisation of extracellular ROS — which drive T cell mitochondrial damage, PD-1 overexpression, and M2 macrophage polarisation — rather than through extracellular NAD⁺ availability. Third, the NADH-rich extracellular environment may directly support immune cell bioenergetics: T lymphocytes with functional mitochondria can potentially utilise extracellular reducing equivalents through membrane redox systems, whereas cancer cells with dysfunctional mitochondria cannot benefit from the same substrates. This differential mirrors the core selectivity principle of the hypothesis.
Antigen release in situ and potential systemic priming (hypothesis). A related consequence follows from the fact that the framework does not remove the tumour but progressively reduces it in situ. Antigen is therefore released within the host rather than excised, in a form determined by the mode of cell death. Cell death by oxidative burst on restoration falls within the category associated with immunogenic cell death — release of calreticulin, HMGB1 and ATP — rather than within the silent apoptotic category, and is therefore a candidate for antigen presentation through dendritic cell maturation in the draining lymph node. The draining node moreover lies outside the perturbed volume, so presentation is spatially as well as temporally separated from the impulse. Repetition would compound this: a first cycle serves principally to expose antigen, subsequent cycles acting on a system already primed. Two qualifications apply to that coupling. Reactive hyperaemia operates over minutes whereas lymphocyte recruitment operates over hours, so the mechanism cannot be transport of cells during the hyperaemic peak itself and must instead be chemokine release and adhesion-molecule expression during that window, with arrival following. And reperfusion recruits neutrophils and polarises macrophages in directions that are not uniformly favourable, so the net sign is an empirical question rather than a deducible one, to be settled by characterisation of the infiltrate at defined intervals across the cycle in an immunocompetent model.
Should systemic priming occur, it would in principle extend to disseminated disease, a mechanism analogous to the abscopal responses occasionally reported after localised radiotherapy. The analogy is imperfect and is drawn for the obstacle it identifies rather than for the similarity of the interventions: antigen release alone is evidently insufficient, since it occurs routinely during radiotherapy while abscopal responses remain rare, and the bottleneck lies downstream in antigen presentation and in the avoidance of tolerance. Two features of the present framework bear on that bottleneck. Antigen release occurs on restoration rather than during the impulse, so it coincides with a microenvironment returning toward normoxia rather than with the suppressed state of the loading phase. And presentation occurs in the draining lymph node, outside the perturbed volume. Whether these features are sufficient is not established: the sequence requires that the oxidative-burst death be immunogenic in the specific sense of calreticulin exposure and HMGB1 release, that dendritic maturation follow, and that the resulting clones reach distant lesions. None of these steps has been measured here, and the proposition is advanced as a hypothesis to be tested — by characterisation of tumour-specific T cell responses in the draining lymph node and in circulation across successive cycles, and by assessment of untreated distant lesions in appropriate models.
Two determinants of immune cell arrival, distinct from the redox argument above, bear on the plausibility of this sequence. The first is acidosis: the acidic tumour microenvironment is itself immunosuppressive, and its transient attenuation during recovery would be expected to lower one barrier to effector function independently of ROS. The second is perfusion. Recruitment of circulating lymphocytes is delivered by blood flow, so the reactive hyperaemia that follows an ischaemic interval should transiently increase the arrival of competent cells at precisely the point in the cycle at which antigen has been released. This links the immunological arm to the same parameter that governs selectivity in the acceptor-subtraction route (Section 5.6), and is measurable by perfusion imaging alongside characterisation of the infiltrate. The effect is expected to be short-lived rather than cumulative: across repeated cycles, oedema and raised interstitial pressure would tend to degrade perfusion rather than improve it (Section 8.2(j)), and tissue replaced by fibrosis is less vascularised than the tissue it replaces.
7.2. The Nocturnal Window as a Physiological Reductive Impulse
The natural circadian cycle features a nocturnal window characterised by: maximal melatonin production (a potent endogenous antioxidant), cortisol nadir (anti-inflammatory), parasympathetic nervous system activation, and, under post-prandial fasting conditions, progressive activation of mild ketosis. This window represents a physiological reductive impulse that can be deliberately enhanced and extended through: extended overnight fasting (14–16 hours), complete environmental darkness, curcumin and EGCG supplementation in the evening window, and avoidance of alcohol (whose hepatic metabolism overloads the NAD⁺/NADH system and generates pro-oxidant acetaldehyde).
7.3. Integrated Preventive Protocol
A conservative preventive approach is proposed at the level of daily habit only. Cyclic intensive protocols combining prolonged fasting with pulsed infusions are deliberately not specified here, for the reasons given in Section 6.3. At the daily level, the nocturnal reductive window described in Section 7.2 can be enhanced and extended to 8–10 hours through intermittent fasting, magnesium supplementation, evening antioxidants, and sleep in complete darkness.
7.4. Delivery Considerations for the Preventive Application
The route of administration for the anti-aging application differs in kind from the oncological one and is not specified in detail here. The oncological proposal under acceptor subtraction is inherently localised, since that route presupposes spatial confinement (Section 8.2(j)); under donor addition it is systemic in distribution, selectivity arising metabolically rather than spatially (Section 5.6). The preventive application has the opposite requirement, since the hormetic renewal described in Section 7.1 is a systemic objective rather than a regional one, and no single tissue is the target.
Two constraints follow. First, a systemic route producing hepatic first-pass exposure rather than a systemic peak would limit delivery to the tissues most susceptible to reverse-electron-transport injury, as noted in Section 8.1(g). Second, and for the same reason, the heart and the central nervous system warrant specific attention in any systemic protocol: both are high-demand oxidative tissues with polarised mitochondria, and both are the tissues in which reperfusion-type injury is best characterised. A systemic reductive impulse intended for hormetic benefit must therefore remain well below the intensity at which the mechanisms of Section 5.1.1 become operative — the therapeutic aim in the preventive setting being adaptive stimulation rather than selective cytotoxicity. The intensity at which that boundary lies is not a fixed quantity: it depends on the same redox buffering reserve that governs selectivity in the oncological setting, and therefore varies between individuals and with age. A stimulus that is tolerable in one individual may exceed the adaptive range in another, and the hormetic response would be expected to follow the biphasic dose–response characteristic of such interventions, in which benefit increases to an optimum and declines thereafter. Establishing where that optimum lies for a given individual, and by what measurement, is precisely what a dedicated treatment of the preventive application would need to address; in the absence of such data no intensity beyond the conservative daily measures of Section 7.3 is proposed here.
Defining these parameters, and the route by which a systemic impulse of controlled intensity could be delivered, falls outside the scope of the present work and is left to a dedicated treatment.
8. Limitations and Future Directions
8.1. Limitations of the Present Hypothesis
The proposal has several limitations that are openly acknowledged:
- (a)
- Absence of specific clinical data: no clinical trials exist that test pulsed NADH administration with the metabolic selectivity rationale described here. The experiences of the Hyperthermia Centre Hannover (8) and Birkmayer (7) use NADH in a different therapeutic framework (general support) without press-pulse logic.
- (b)
- Pharmacokinetics of exogenous NADH: the intracellular bioavailability of intravenously administered NADH is not fully characterised. NADH could be metabolized in plasma before reaching target cells. Dedicated pharmacokinetic studies are necessary. The fate of the fraction oxidised to NAD⁺ in plasma requires comment. Extracellular NAD⁺ is rapidly hydrolysed by ectonucleotidases, principally CD38 and CD157, to nicotinamide and ADP-ribose, with a plasma half-life on the order of minutes (44), and CD38 is overexpressed in the tumour microenvironment. This kinetic argument suggests that transient elevation is unlikely to sustain tumour glycolysis, but it does not resolve the broader concern raised in Section 2.2, and the position taken in this work is the conservative one: systemic elevation of circulating NAD⁺ is treated as a potential liability rather than as a secondary benefit. This is a further argument against NADH as the vehicle of choice.
- (c)
- Tumour heterogeneity: tumours differ in residual mitochondrial competence, and the framework predicts that this determines which mechanism engages rather than whether the approach works at all (Section 5.1.1). The practical difficulty is that neither position on the axis is directly measurable in patients with current imaging. FDG-PET indicates glycolytic flux but not proton-pumping capacity, and the predicted zone of intermediate resistance would not be identifiable by it. Patient stratification would require ex vivo measurement on biopsy material. The oligomycin-sensitive fraction of ATP production identified in Supplementary Material S1 is measurable on such material by extracellular flux analysis.
- (d)
- Therapeutic window: the distance between the dose effective against cancer cells and the dose toxic to healthy cells — considering the respiratory control mechanism that also limits the clearance capacity of healthy cells — could be narrow. Only preclinical experimentation can define this window.
- (e)
- Interaction with conventional therapies: the effect of the reductive impulse on cells treated with chemotherapy, radiotherapy, or immunotherapy is unknown and requires specific study. Of particular interest would be the combination with PARP inhibitors (e.g., olaparib), which deplete intracellular NAD⁺ through a complementary mechanism.
- (f)
- Need for structural turnover: the administration of exogenous reducing equivalents does not repair damaged respiratory complexes. Its effect is to bypass metabolic bottlenecks and, through cyclic impulses, to stimulate the mitophagy and mitochondrial biogenesis that replace structurally compromised components.
- (g)
- Vulnerability of healthy post-ischaemic-type tissue. The mechanism proposed in Section 5.1.1 and Section 5.6 is formally the same process that mediates reperfusion injury in the heart and brain, where RET-derived superoxide accounts for the majority of reactive oxygen species generated in the early reperfusion phase (47). Cardiomyocytes and neurons are high-demand oxidative tissues with polarised mitochondria and are therefore candidate sites of dose-limiting toxicity. Selectivity cannot be assumed on theoretical grounds and must be demonstrated; any in vivo programme should include cardiomyocytes and neurons among control cell types from the outset. Pharmacological mitigation is conceivable — inhibition of Complex II with dimethyl malonate, or of Complex I, is protective in experimental ischaemia-reperfusion (47) — but carries an intrinsic tension, since systemic administration of such agents would also suppress the intended antitumour mechanism. Any such strategy would require temporal or regional separation from the therapeutic pulse and cannot be assumed to be compatible with it. For the anti-aging application discussed in Section 7.4, this constraint is less severe, since routes producing hepatic first-pass exposure rather than a systemic peak would limit delivery to the tissues most susceptible to RET-mediated injury.
- (h)
- Possible pro-angiogenic counter-effect. An elevated NADH/NAD⁺ ratio is associated with stabilisation of HIF-1α in models of pseudohypoxia, a state characterised by activation of hypoxia-response pathways under normoxic conditions and driven by reductive stress (55). Since HIF-1α stabilisation upregulates VEGF and the angiogenic programme, a reductive impulse could in principle oppose the reduction in inflammatory and proliferative signalling anticipated in Section 7.1. The transient nature of the proposed perturbation makes the quantitative relevance of this effect unpredictable a priori. Direct measurement of HIF-1α and VEGF across the pulse-recovery cycle should therefore be included in the preclinical programme, and a positive finding would constitute a substantive argument against the approach.
- (i)
- Cycle-dependent drift in proton conductance. Section 5.1.1 treats proton conductance as a fixed property of the cell. It is not. The basal component depends on the phospholipid composition of the inner membrane and on the abundance of the adenine nucleotide translocase (63, 64), and the inducible component is activated by superoxide and by 4-hydroxynonenal (67, 68) — products the impulse itself generates under donor addition. Repeated cycles may therefore modify the parameter they act upon. Since mitophagy and PGC-1α-mediated biogenesis replace peroxidised membranes in cells competent for mitochondrial turnover and do not in cells that are not, the drift is predicted to run in opposite directions in the two populations; the prediction is stated by turnover competence rather than by transformation status, since mitophagic competence is not uniformly absent in tumours and varies between them.
The sign of the drift is unfavourable in one region of the axis only. In the transformed population, rising conductance bounds membrane potential and progressively attenuates Mechanism A, while displacing the cell toward the second zone of resistance identified in Section 5.1.1, since an uncoupled phenotype clears the load through the chain and sustains a higher glycolytic flux and LDH capacity besides (72, 73). The concern is therefore confined to the hyperpolarised phenotype retaining respiratory competence, which is the same region in which Mechanism A is most favoured; at the compromised end conductance is low and the question does not arise. In healthy tissue the drift runs the other way and is favourable rather than otherwise: proton conductance there adds to the flux that discharges the accumulated gradient, shortening residence in the permissive condition in cells that already possess the ATP synthase throughput to do so, and therefore widening the therapeutic window on the side of safety.
Three considerations bound the concern. The drift is phenotypic and reversible rather than heritable, so it does not constitute clonal selection. The inducible component requires a high membrane potential to operate (68), so it relaxes during the recovery interval rather than persisting, which confines any cumulative effect to the basal component. And the acceptor-subtraction route is not subject to the feedback on the same timescale, for the reason given in Section 5.6, so it is predicted to be the less affected of the two routes in precisely the phenotype where the concern arises (Section 5.5). The net effect on the therapeutic window cannot be predicted a priori, and is measurable directly, since conductance is obtained from the same extracellular flux trace as the other baseline parameters. Should the drift be observed, it would argue for a sequenced regime — early cycles exploiting Mechanism A while potential remains high, later cycles shifting toward Mechanism B through intensified substrate restriction, inhibition of inducible conductance, or the electrochemical route — rather than for repetition of an identical cycle.
8.2. Future Directions
- (a)
- Preclinical in vitro studies with the protocol described in Section 6.1 to validate the selectivity of the reductive impulse, with specific measurement of the simultaneous blockade of glycolysis, OxPhos, and mSLP.
- (b)
- Development of NADH formulations in liposomes or nanoparticles to improve intracellular delivery.
- (c)
- Combined study of pulsed reductive load with PARP inhibitors, which deplete intracellular NAD⁺ through a complementary mechanism.
- (d)
- Systematic comparison of vehicles by the compartment they reach — cytosolic versus mitochondrial — using the clamp comparators and the compartment-targeted NADH oxidases described in Section 6.1 (80, 81), to establish which compartment governs the effect.
- (e)
- Development of predictive response biomarkers based on tumour metabolic profile (NAD⁺/NADH ratio, complex I expression, LDH activity, succinate export as indicator of mSLP dependence).
- (f)
- Comparative evaluation of different modalities for exogenous reducing equivalent delivery (NADH, ubiquinol, H₂, and future catalytic redox vehicles) within the press-pulse protocol.
- (g)
- Investigation of the potential immunometabolic effects of reductive impulses on tumour-associated macrophage polarisation and T lymphocyte function in the tumour microenvironment.
- (h)
- Investigation of the combination of pulsed reducing equivalent infusions with CD38 inhibitors (e.g., daratumumab, already approved for multiple myeloma). CD38 overexpression in the tumour microenvironment depletes extracellular NAD⁺, contributing to T cell exhaustion. Inhibition of CD38 during the reductive impulse could simultaneously preserve extracellular NAD⁺ for immune cell function while the reductive load disrupts tumour metabolism through the mechanisms of Section 5.1.1 — creating a three-pronged attack combining metabolic blockade, immune restoration via CD38 inhibition, and immune unmasking via ROS neutralisation.
- (i)
- Electrochemical implementation of acceptor subtraction. Section 5.6 sets out the mechanism and the origin of selectivity for this route; what follows concerns how oxygen removal might be achieved and what would have to be measured to establish whether the required condition is attainable. Cathodic polarisation reduces dissolved oxygen, consuming it rather than displacing it, and thus offers a means of imposing the condition locally and reversibly, with timing under direct control rather than governed by distribution volume or perfusion. An endogenous redox mediator, ascorbate being the most tractable, has a role that should be stated precisely: it does not deliver the reductive load, since no extracellular species is a sufficiently strong reductant for that purpose (Section 5.5). Its contributions are three, all accessory and all real. It buffers charge at the cathode, limiting the hydroxide generation that otherwise constrains admissible current density. It intercepts the reactive species transiently produced while oxygen is being consumed — a self-limiting phase, since their generation ceases once the substrate is exhausted. And it attenuates microenvironmental ROS with the consequences discussed in Section 7.1, with the further consideration that tumour ascorbate content correlates inversely with HIF-1 pathway activation and with VEGF expression (59, 60), so mediator supply may act against the counter-effect identified in Section 8.1(h). Local availability cannot be assumed: tumour tissue ascorbate is generally lower than in matched adjacent normal tissue and decreases with tumour grade (59, 60), consistent with preferential consumption in an oxidising microenvironment and with compromised delivery through poorly vascularised tissue (61). The mediator must therefore be supplied rather than found, which is the rationale for combination with high-dose intravenous administration. A qualification of the opposite sign must accompany this proposal, since it concerns the best-documented property of the compound. At the plasma concentrations reached by high-dose intravenous administration, ascorbate acts as a pro-oxidant rather than as an antioxidant, generating extracellular hydrogen peroxide with the ascorbate radical as intermediate, and this is the accepted mechanism of its selective cytotoxicity toward tumour cells (83, 84). The apparent contradiction with the reductive framing of this work is resolved by scale and by phase rather than by denial, along the lines set out in Section 8.2(k): the mediator role proposed here operates at the electrode, within a volume in which oxygen is being removed and at concentrations set by local supply, whereas the pro-oxidant action is a bulk extracellular phenomenon at millimolar concentrations in the presence of oxygen. The two may converge rather than conflict, since the cathode itself generates hydrogen peroxide through the two-electron pathway of oxygen reduction, and peroxide from either source acts on the same compartment. What follows is operational: the intended mediator concentration and the pro-oxidant threshold must be separated explicitly in any protocol, and the contribution of ascorbate-derived hydrogen peroxide is a confounder to be measured rather than a term that can be assumed absent.
Intensity and duration are separate variables and act on different things: intensity determines whether, and within what radius, oxygen falls below the functional threshold of Complex IV, while duration determines which mechanism operates within that radius. Four regimes follow, of which only the middle two approach the target condition. Below the threshold for volumetric depletion, no tissue anoxia is established and no mechanism of Section 5.1.1 is engaged, although oxygen is depleted within the diffusion layer at the electrode surface wherever the local limiting current is exceeded, which is the condition on which the thiol contribution of Section 7.1 depends. The charge delivered per unit volume of tissue is correspondingly small, being distributed over a large electrode area and a large treated volume with perfusion and bicarbonate resupply intact, so hydroxide generation remains within the interstitial buffering capacity and the pH excursion is negligible by the estimates of Supplementary Material S2; the constraints that bound the higher regimes therefore do not apply, and application may be regional, prolonged and repeated. What such a regime provides is the reduction of interstitial oxidative load discussed in Section 7.1, with mediator turnover as described above. This is the electrochemical counterpart of the dietary press: continuous, of low intensity, acting on the chronic oxidative and inflammatory background and on the barrier to effector function rather than producing selective cytotoxicity. Its relevance is greatest where the pulse is least effective — in the predominantly fermentative phenotype, for which the framework predicts arrest of the mitochondrial arm alone (Section 5.6.1) and for which conditioning of the microenvironment, combined with an agent supplying the antigen that conditioning does not, may be the more appropriate objective. At depletion threshold, a brief withdrawal terminates while membrane potential is still sustained, so reoxygenation encounters a saturated quinone pool at elevated potential and Mechanism A follows. A prolonged withdrawal at the same current allows proton leak to dissipate the potential, so the RET window is not entered on restoration, while arrest of matrix NAD⁺ re-oxidation has meanwhile engaged the mitochondrial arm of Mechanism B. Neither duration reaches the cytosolic arm, for the reason given in Section 5.6.1. A fourth regime lies above the rate at which oxygen diffuses to the electrode surface. There the cathodic reaction proceeds by reduction of water and of the endogenous reducible solutes, generating hydroxide without further depletion of oxygen, so additional charge contributes alkalinisation together with the thiol reduction that Section 7.1 assigns to the press and that is unwanted in this phase. Since alkalinisation increases the driving force for proton-coupled lactate export and thereby assists cytosolic NAD⁺ regeneration, that regime is not merely unproductive but counterproductive — a further and independent argument for the low duty cycle that Supplementary Material S2 derives from pH drift alone. The transition between the third and fourth regimes is set by mass transport rather than by any electrical parameter, and is therefore the quantity that determines the useful radius of a single source.
A third argument for brevity follows from the faradaic competition itself, and is stated here in the form that competition actually takes. Reduction of dissolved oxygen is limited by transport to the electrode surface, so it draws a current ceiling set by the local oxygen concentration and by the diffusion layer rather than a fixed share of the applied current; current in excess of that ceiling reaches water and the endogenous reducible solutes, cystine among them. Two consequences follow and they are distinguished by scale. Thiol reduction begins as soon as the limiting current is exceeded at the surface, within a diffusion layer of tens of micrometres, and in that configuration it is the intended effect of the press described in Section 7.1. It becomes a liability only when the depletion front propagates into the treated volume, since from that point the reduction proceeds in the tissue in which the discharge is intended and reinforces the antioxidant buffer that the discharge is meant to overcome. Current continued beyond the establishment of volumetric depletion therefore works against the mechanism, which is a third and independent argument converging on short duration, alongside cathodic pH drift and the inducible conductance feedback of Section 5.1.1.
Within the productive range, two regimes are conceivable, and they may be complementary rather than alternative. A distributed configuration keeps local current density, and hence oxygen depletion, moderate; selectivity then rests principally on the perfusional asymmetry, with attenuated ischaemia and correspondingly reduced injury to surrounding tissue. A focused configuration concentrates current density to produce deeper local ischaemia. The charge required to deplete dissolved oxygen is considerably smaller than that required to produce the extremes of pH associated with coagulative injury, so an intermediate window may exist in which oxygen is consumed while the local vasculature remains intact — a condition that is desirable rather than incidental, since rapid reoxygenation on cessation is what drives the discharge phase. Whether such a window is accessible in tissue, given that current density falls steeply with distance from the source, is an empirical question; low duty-cycle pulsing, in which brief high-density pulses are separated by intervals allowing buffer-mediated pH recovery, is the most plausible route to separating the two thresholds. In the focused regime, oxygen depletion is imposed by current density rather than permitted by poor perfusion, so ischaemia is established irrespective of local blood flow; selectivity there rests on spatial confinement and on the succinate differential of Section 5.1.1. Alternation between the two configurations across successive cycles may be more effective than either alone, since they act on different variables, and would address the limited radius of any single focused application in tumours exceeding that dimension by allowing the site of discharge to be displaced between cycles. The two regimes are also expected to diverge across repeated cycles in opposite directions: in the focused regime, if not carefully calibrated, local oedema and raised interstitial pressure would progressively degrade perfusion, deepening the loading phase while weakening the discharge, so that the approach is self-limiting with an optimal number of cycles; in the distributed regime, mild inflammatory vasodilatation would tend to improve perfusion while making oxygen depletion harder to establish. Neither drift is predictable a priori, and inter-cycle interval and regime selection would need to be guided by perfusion measurement between cycles. Five limitations are specific to this route and are stated without attenuation. Hypoxia stabilises HIF-1α through the canonical pathway, with angiogenic consequences; the effect is bounded by the transient and localised nature of the perturbation, and arises in tissue where the pathway is already constitutively active (Section 3.1), but it is not abolished. Clonal selection requires separate treatment, and the argument that bioenergetic collapse is not a selective regime — that no phenotype survives the absence of ATP — does not apply here, since what this route imposes is cyclic hypoxia and reoxygenation rather than sustained withdrawal of ATP. Cyclic hypoxia is among the best-characterised selective pressures in experimental oncology, acting through HIF-mediated transcriptional programmes rather than through survival of an energy deficit, and is associated with genomic instability, epithelial-mesenchymal transition, resistance to radiation and to cytotoxic agents, and increased metastatic potential. The concern is compounded rather than relieved by the position taken in Section 5.1.1: if the reprogrammed low-flux state described by Jin et al. (57) is an alternative outcome to collapse rather than a stage preceding it, then deep quiescence is not incompatible with tumour growth but compatible with regrowth once treatment ends. Three considerations bound the concern without dissolving it. The phenotypes in question are induced and reversible rather than heritably selected. The perturbation is confined to the treated volume and to the duration of the impulse, whereas the models establishing the selective effect employ repeated cycles over days to weeks. And the discharge phase, which is the intended cytotoxic event, occurs on reoxygenation, so the same cycle that constitutes the selective pressure also delivers the killing. Whether the net balance favours cytotoxicity or selection is an empirical question and is the principal risk specific to this route. It is answered by serial characterisation of the surviving population across cycles — HIF target expression, invasive and clonogenic capacity, and response to a subsequent cycle — in an orthotopic immunocompetent model, and a positive finding would be grounds for abandoning the route rather than for adjusting it. Hypoxia is immunosuppressive during the impulse, which the pulsed structure confines to that phase; sustained immune activation within a tumour is in any case dysfunctional, so cyclic suppression and restoration may be preferable to persistent low-grade engagement. Cathodic alkalinisation constrains admissible current density. The constraint is moreover not only one of toxicity. Protonmotive force has two terms, and the pH gradient across the inner membrane contributes to the force on which reverse electron transport depends; an imposed drift in interstitial and hence cytosolic pH perturbs that term directly, in the same volume and over the same interval in which the mechanism is intended to operate. Whether the perturbation adds to or subtracts from the force is not predictable from the drift alone and requires the paired measurement of interstitial pH and membrane potential specified in Section 9. Supplementary Material S2 estimates that constraint: sustaining oxygen depletion against perfusional resupply requires volumetric current densities of 1–4 mA/cm³, with a corresponding pH drift of 0.03–0.10 units per minute. Whether that regime is separated from the one at which cathodic pH approaches 12 and coagulative necrosis follows depends on the treated radius per source rather than on the volumetric density alone, since the two are quantities of different dimensions: the separation holds at radii of a few millimetres per source and closes as a single source is asked to cover more. The limiting variable is therefore impulse duration rather than intensity, which establishes low duty-cycle pulsing as a structural feature of the regime rather than an expedient. The estimate rests on mean tissue parameters drawn from animal and xenograft data and on an assumed interstitial buffering capacity, and the local pH in the immediate vicinity of the tip is higher than any acceptable mean. And reperfusion generates acute inflammation; whether this is detrimental or contributes through immunogenic cell death is not established, though a locally confined inflammatory injury compares favourably with the systemic toxicity of conventional cytotoxic therapy. The purpose here is to identify the measurements that would decide these questions: interstitial pH as a function of distance from the source and of time; interstitial redox potential and mediator consumption; local oxygen tension relative to the Km of cytochrome c oxidase; effective interstitial buffering capacity; and the comparative kinetics of pH re-equilibration and of oxygen return after cessation, which determine the optimal duty cycle. Each should be compared between tumour tissue and healthy tissue equidistant from the source. No device is proposed here: the dimensional estimates in Supplementary Material S2 serve to establish that the regime is accessible, not to specify a design.
- (j)
- Catalytic regeneration of consumed reducing vehicles. A corollary follows for antioxidant therapy generally and is independent of the oncological hypothesis advanced here. The stoichiometric limitation identified in Section 4 — that an antioxidant donating its electron becomes a radical and is consumed — is a property of administered molecules rather than of the redox couple itself. A cathode that reduces the oxidised member of such a couple converts it from a consumed reagent into a carrier that cycles, with the electrode rather than the molecule as the electron source, and transport to the electrode is convective rather than diffusive since the carrier circulates, so the radius of this contribution is governed by perfusion rather than by the diffusion layer that bounds oxygen depletion. A third qualification is required and follows from the chemistry set out in Section 4.2, since it bears on the proposal rather than merely accompanying it. The pro-oxidant action of ascorbate resides in its reduced form, which reduces ferric iron and supplies hydrogen peroxide by autoxidation. A cathode that regenerates the reduced member of the couple therefore regenerates the pro-oxidant species as well as the carrier, and the stoichiometric limitation is relieved at the cost of sustaining rather than exhausting that chemistry. The resolution is spatial and temporal rather than chemical, and it is the same structure as in (l). The Fenton sequence requires molecular oxygen, both as the source of hydrogen peroxide through autoxidation and as the substrate of the superoxide route; within the volume that cathodic polarisation has rendered anoxic, that requirement is not met. Regeneration of the mediator is accordingly admissible within the depletion window and not outside it, and the two functions of the electrode — consuming oxygen and reducing the carrier — are mutually enabling rather than merely concurrent. Operationally this converts the mediator contribution from a continuous adjunct into one confined to the same duty cycle as the impulse itself, and it predicts that mediator supplied before depletion is established, or persisting after reoxygenation, acts in the pro-oxidant direction. The prediction is testable by measuring interstitial hydroxyl-radical adducts and labile iron with and without mediator, inside and outside the depleted volume. Two qualifications restrict the claim. Dehydroascorbate is reduced with high capacity by erythrocytes, so regeneration is already substantial wherever blood reaches, and the contribution of an electrode is correspondingly limited to tissue in which that capacity is least available — which is also where tumour ascorbate content is reported to be lowest (59–61). And dehydroascorbate is labile at physiological pH, with a half-life of minutes, so the cycle carries a first-order loss of carrier rather than closing on itself. The faradaic yield for the intended reduction, as a function of electrode potential and material and in the presence and absence of dissolved oxygen, is the measurement that would establish whether the contribution is quantitatively significant; potentiostatic rather than galvanostatic control is required for it, which applies equally to the oxygen-depletion regime above.
- (k)
- Electrochemical donor addition through a membrane-permeant mediator. The thermodynamic constraint stated in Section 5.5 — that no endogenous extracellular species is a sufficiently strong reductant to reduce NAD⁺ across the membrane — does not bind an electrode, whose potential is imposed rather than inherited from the surrounding chemistry. A mediator reduced at a sufficiently negative potential, permeant to the plasma membrane and oxidised intracellularly by an NAD-dependent dehydrogenase, would constitute donor addition by electrochemical means and would be the only route by which the cytosolic arm of Mechanism B could be reached without an intratissue anode. The requirement is a specification rather than a candidate: a lipophilic mediator with a potential below that of the NAD⁺/NADH couple, recognised by a dehydrogenase, and unreactive toward molecular oxygen. The known lipophilic mediators in that potential range are viologens, which transfer electrons indiscriminately and preferentially to oxygen, generating superoxide rather than reduced pyridine nucleotide; the proposition is accordingly advanced as a design target and not as an available implementation. Two conditions would favour it if such a mediator existed: within a volume already rendered anoxic, competition from oxygen is removed, so the two functions of the electrode are mutually enabling; and direct electrochemical reduction of NAD⁺ itself is not an alternative, since it yields predominantly enzymatically inactive dimers rather than the 1,4-isomer.
9. Conclusions
This work proposes a reframing of how NAD⁺/NADH metabolism might be manipulated therapeutically in cancer and aging. Rather than administering NAD⁺, as prevails in anti-aging practice, or depleting it pharmacologically, as prevails in oncology, it proposes the pulsed delivery of exogenous reducing equivalents, and locates the therapeutic variable in the recovery interval rather than in the dose.
Three propositions constitute the substantive content of the framework.
The first is that selectivity arises from differential redox buffering capacity rather than from any specific mitochondrial defect. A healthy cell possesses simultaneously the respiratory reserve to dispose of an imposed reductive load and the gradient-discharging flux required to discharge the resulting proton gradient. Neither property alone confers protection; their conjunction does. Transformed cells are deficient in one or the other, and which deficiency applies determines which mechanism engages: reverse electron transport at Complex I where proton-pumping capacity is retained, or limitation of free NAD⁺ where it is not — arresting mitochondrial substrate-level phosphorylation in the matrix, and glycolysis in the cytosol, in two arms that the two routes do not reach equivalently. Because a cell may sustain membrane potential without respiring, these properties are independent rather than the two ends of a single axis, and phenotypes are placed on a plane accordingly. The configuration in which both are retained is resistant to donor addition, which is stated explicitly as a way the model can fail; it is not, however, resistant to acceptor subtraction, since neither escape survives removal of the terminal acceptor. The framework therefore predicts route-dependent rather than uniform efficacy.
The second is that intermittency is a therapeutic parameter rather than a scheduling convenience. Intermittent dosing has been used clinically with Complex I inhibitors, but as a means of mitigating toxicity rather than as a mechanism of selectivity; the duration of the recovery interval has not, to our knowledge, been optimised against differential recovery kinetics. If the two cell populations return to their redox setpoint at different rates, the pause is where selectivity is generated, and the Phase I programme that terminated on grounds of a narrow therapeutic window (56) may have optimised the wrong variable.
The third is that the principle is bound neither to a particular molecular vehicle nor to a particular direction of intervention. Where the chain retains proton-pumping capacity, the proximate target is a thermodynamic condition — an over-reduced coenzyme Q pool sustained at elevated membrane potential — and because under normoxic operation that pool has several dehydrogenase inputs and a single oxygen-dependent outlet, that condition is approachable in two directions: addition of the electron donor, or subtraction of the terminal acceptor. Where it does not, the target is instead the availability of free NAD⁺, in two compartments whose terminal acceptors differ — oxygen in the matrix, pyruvate in the cytosol — and which the two routes therefore do not reach equivalently. The first route is pharmacological and is constrained by delivery, by shuttle capacity and by cytosolic LDH; the second requires no delivery at all, since the reductive load is generated by the cell’s own substrates once the outlet is closed, but its selectivity is perfusional and spatial rather than metabolic, and it does not reach the cytosolic arm at any intensity. NADH is discussed throughout as the illustrative donor, on grounds of native enzymatic recognition and existing clinical precedent, but it is explicitly not the optimal one. Two distinct arguments favour combining the routes, and they should not be conflated. Because they act on opposite terms of the same balance, their effect on the reduction state of the quinone pool is predicted to be multiplicative rather than additive, which is an argument about intensity. And because they fail in different places — donor addition where the chain retains respiratory reserve, acceptor subtraction where perfusion restores the terminal acceptor — their zones of resistance are largely disjoint, which is an argument about coverage. The second is the stronger of the two, and it predicts that the ranking of susceptibility across a panel of lines should differ between the routes rather than merely shift in magnitude.
The framework is stated in falsifiable form, and its principal vulnerabilities are identified rather than deferred. Cytosolic lactate dehydrogenase provides a route by which NAD⁺ regeneration proceeds without mitochondrial participation. It protects the cytosolic arm of Mechanism B directly and acts as an upstream filter on the load reaching the matrix under donor addition, but it has no access to the compartment in which the mitochondrial arm operates and does not protect against it; this is the reason combination with LDH inhibition is proposed rather than offered as an enhancement. Mitochondrial proton leak provides a second route, acting one step downstream and consuming nothing: it relieves the back-pressure on which the block depends, bounds the membrane potential and therefore attenuates the yield of Mechanism A, and unlike lactate dehydrogenase it has no substrate to exhaust. It is an escape from donor addition and not from the framework: a conductance sufficient to dissipate the load also relieves the back-pressure on the chain, so such a cell clears the load while never sustaining potential, and it therefore occupies a second zone of resistance specific to that route. Neither zone survives withdrawal of the terminal acceptor, which is a further instance of the complementarity in domain described above, and the leak remains the reason a short and steep impulse is preferred to a prolonged one. Reverse electron transport is the same process that mediates reperfusion injury in the heart and brain, so the mechanism invoked for antitumour selectivity is also a mechanism of injury in high-demand oxidative tissue, and selectivity must be demonstrated rather than assumed. Reductive stress has been shown to stabilise HIF-1α in models of pseudohypoxia, raising the possibility of a pro-angiogenic counter-effect. And two published findings bear directly on the hypothesis: a reduced cytosolic redox state has been shown to protect against oxidative stress-induced apoptosis (54), and agents that oxidise the NAD⁺/NADH ratio have been identified as selectively cytotoxic to cancer cells (52). The framework is compatible with both only under a specific reading — that the reductive phase constitutes loading and the oxidative event constitutes discharge, and that the relevant compartment is mitochondrial rather than cytosolic — and that reading is itself an experimental claim.
Each of these propositions can be tested with existing reagents and instrumentation, and the programme set out in Section 6.1 is designed so that a negative result is informative. In particular, the prediction that a mitochondrial reductive clamp is injurious while a cytosolic clamp is protective constitutes a single measurement capable of invalidating the framework as stated.
If validated, the approach would define a class of metabolic interventions operating on redox flux control rather than on pool concentration, and on the kinetics of recovery rather than on the magnitude of the perturbation. If not, the measurements proposed here would still resolve a question that the existing literature leaves open: whether transformed and healthy cells differ in how quickly they return to redox homeostasis after a defined perturbation. That question is worth answering irrespective of the therapeutic hypothesis that motivates it.
Supplementary Materials
The following supporting information can be downloaded at website of this paper posted on Preprints.org.
Funding
This work received no external funding.
Use of Artificial Intelligence
The author used Claude (Anthropic) as an AI-assisted writing tool for literature synthesis, text drafting, translation and figure preparation. All scientific hypotheses, conceptual framework, and critical analysis are the original intellectual contribution of the author. The author takes full responsibility for the content of the manuscript.
Acknowledgments
The author thanks the scientific community for the foundational work on the metabolic theory of cancer and NAD⁺ biology that made the formulation of the hypotheses presented here possible. In particular the author is grateful to Prof. Thomas N. Seyfried (Boston College) for valuable feedback on mitochondrial substrate level phosphorylation and the role of glutaminolysis in cancer cell ATP production, which strengthened the manuscript.
Conflict of Interest
The author declares no conflicts of interest.
References
- 1.Warburg O, Wind F, Negelein E. The metabolism of tumors in the body. J Gen Physiol. 1927;8(6):519-530. [CrossRef]
- 1b.Warburg O. On the origin of cancer cells. Science. 1956;123(3191):309-314. [CrossRef]
- 2.Seyfried TN. Cancer as a Metabolic Disease: On the Origin, Management, and Prevention of Cancer. Hoboken, NJ: Wiley; 2012.
- 3.López-Otín C, Blasco MA, Partridge L, Serrano M, Kroemer G. Hallmarks of aging: an expanding universe. Cell. 2023;186(2):243-278. [CrossRef]
- 4.Massudi H, Grant R, Braidy N, Guest J, Farnsworth B, Guillemin GJ. Age-associated changes in oxidative stress and NAD+ metabolism in human tissue. PLoS One. 2012;7(7):e42357. [CrossRef]
- 5.Grant R, Berg J, Mestayer R, Braidy N, Bennett J, Broom S, Watson J. A pilot study investigating changes in the human plasma and urine NAD+ metabolome during a 6 hour intravenous infusion of NAD+. Front Aging Neurosci. 2019;11:257. [CrossRef]
- 6.Yaku K, Okabe K, Hikosaka K, Nakagawa T. NAD metabolism in cancer therapeutics. Front Oncol. 2018;8:622. [CrossRef]
- 7.Birkmayer JGD, Vrecko C, Volc D, Birkmayer W. Nicotinamide adenine dinucleotide (NADH) — a new therapeutic approach to Parkinson’s disease. Comparison of oral and parenteral application. Acta Neurol Scand Suppl. 1993;146:32-35. [CrossRef]
- 8.Hyperthermia Centre Hannover. NADH infusions in oncology [Internet]. Hannover, Germany. Available from: https://www.hyperthermia-centre-hannover.com [cited 2026 Apr]. Commercial clinic website; no peer-reviewed data.
- 9.Seyfried TN, Yu G, Maroon JC, D’Agostino DP. Press-pulse: a novel therapeutic strategy for the metabolic management of cancer. Nutr Metab (Lond). 2017;14:19. [CrossRef]
- 10.Vander Heiden MG, Cantley LC, Thompson CB. Understanding the Warburg effect: the metabolic requirements of cell proliferation. Science. 2009;324(5930):1029-1033. [CrossRef]
- 11.Verdin E. NAD+ in aging, metabolism, and neurodegeneration. Science. 2015;350(6265):1208-1213. [CrossRef]
- 12.Seyfried TN, Lee DC, Duraj T, Ta NL, Mukherjee P, Kiebish M, Arismendi-Morillo G, Chinopoulos C. The Warburg hypothesis and the emergence of the mitochondrial metabolic theory of cancer. J Bioenerg Biomembr. 2025;57(2-3):57-83. [CrossRef]
- 13.Lee DC, Ta L, Mukherjee P, Duraj T, Domin M, Greenwood B, Karmacharya S, Narain NR, Kiebish M, Chinopoulos C, Seyfried TN. Amino acid and glucose fermentation maintain ATP content in mouse and human malignant glioma cells. ASN Neuro. 2024;16(1):2422268. [CrossRef]
- 14.Lucena-Cacace A, Otero-Albiol D, Jimenez-Garcia MP, Muñoz-Galvan S, Carnero A. NAMPT overexpression induces cancer stemness and defines a novel tumor signature for glioma prognosis. Oncotarget. 2017;8(59):99514-99530. [CrossRef]
- 15.Hasmann M, Schemainda I. FK866, a highly specific noncompetitive inhibitor of nicotinamide phosphoribosyltransferase, represents a novel mechanism for induction of tumor cell apoptosis. Cancer Res. 2003;63(21):7436-7442.
- 16.Sabharwal SS, Schumacker PT. Mitochondrial ROS in cancer: initiators, amplifiers or an Achilles’ heel? Nat Rev Cancer. 2014;14(11):709-721. [CrossRef]
- 17.Mantovani A, Allavena P, Sica A, Balkwill F. Cancer-related inflammation. Nature. 2008;454(7203):436-444. [CrossRef]
- 18.Morré DJ, Morré DM. ECTO-NOX Proteins: Growth, Cancer, and Aging. New York: Springer; 2013.
- 19.Lewerenz J, Hewett SJ, Huang Y, Lambros M, Gout PW, Kalivas PW, Massie A, Smolders I, Methner A, Pergande M, Smith SB, Ganapathy V, Maher P. The cystine/glutamate antiporter system xc- in health and disease. Antioxid Redox Signal. 2013;18(5):522-555. [CrossRef]
- 20.Paulsen CE, Carroll KS. Cysteine-mediated redox signaling: chemistry, biology, and tools for discovery. Chem Rev. 2013;113(7):4633-4679. [CrossRef]
- 21.Bienert GP, Schjoerring JK, Jahn TP. Membrane transport of hydrogen peroxide. Biochim Biophys Acta. 2006;1758(8):994-1003. [CrossRef]
- 22.Halestrap AP, Wilson MC. The monocarboxylate transporter family — role and regulation. IUBMB Life. 2012;64(2):109-119. [CrossRef]
- 23.Aasen T, Mesnil M, Naus CC, Lampe PD, Laird DW. Gap junctions and cancer: communicating for 50 years. Nat Rev Cancer. 2016;16(12):775-788. [CrossRef]
- 24.Xiao W, Loscalzo J. Metabolic responses to reductive stress. Antioxid Redox Signal. 2020;32(20):1330-1347. [CrossRef]
- 25.Aon MA, Cortassa S, O’Rourke B. Redox-optimized ROS balance: a unifying hypothesis. Biochim Biophys Acta. 2010;1797(6-7):865-877. [CrossRef]
- 26.Halliwell B. The antioxidant paradox: less paradoxical now? Br J Clin Pharmacol. 2013;75(3):637-644. [CrossRef]
- 27.Carr AC, Frei B. Toward a new recommended dietary allowance for vitamin C based on antioxidant and health effects in humans. Am J Clin Nutr. 1999;69(6):1086-1107. [CrossRef]
- 28.Traber MG, Atkinson J. Vitamin E, antioxidant and nothing more. Free Radic Biol Med. 2007;43(1):4-15. [CrossRef]
- 29.The Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med. 1994;330(17):1029-1035. [CrossRef]
- 30.Klein EA, Thompson IM Jr, Tangen CM, Crowley JJ, Lucia MS, Goodman PJ, Minasian LM, Ford LG, Parnes HL, Gaziano JM, Karp DD, Lieber MM, Walther PJ, Klotz L, Parsons JK, Chin JL, Darke AK, Lippman SM, Goodman GE, Meyskens FL Jr, Baker LH. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA. 2011;306(16):1549-1556. [CrossRef]
- 31.Murphy MP, Smith RAJ. Targeting antioxidants to mitochondria by conjugation to lipophilic cations. Annu Rev Pharmacol Toxicol. 2007;47:629-656. [CrossRef]
- 32.Skulachev VP. An attempt to prevent senescence: a mitochondrial approach. Biochim Biophys Acta. 2009;1787(5):437-461. [CrossRef]
- 33.Chance B, Williams GR. Respiratory enzymes in oxidative phosphorylation. III. The steady state. J Biol Chem. 1955;217(1):409-427.
- 34.Weiss-Sadan T, Ge M, Hayashi M, Gohar M, Yao CH, de Groot A, Harry S, Carlin A, Fischer H, Shi L, Wei TY, Adelmann CH, Wolf K, Vornbäumen T, Dürr BR, Takahashi M, Richter M, Zhang J, Yang TY, Vijay V, Fisher DE, Hata AN, Haigis MC, Mostoslavsky R, Bardeesy N, Papagiannakopoulos T, Bar-Peled L. NRF2 activation induces NADH-reductive stress, providing a metabolic vulnerability in lung cancer. Cell Metab. 2023;35(3):487-503.e7. [CrossRef]
- 35.Joiner MC, van der Kogel AJ, eds. Basic Clinical Radiobiology. 5th ed. Boca Raton: CRC Press; 2018.
- 36.Sonveaux P, Végran F, Schroeder T, Wergin MC, Verrax J, Rabbani ZN, De Saedeleer CJ, Kennedy KM, Diepart C, Jordan BF, Kelley MJ, Gallez B, Wahl ML, Feron O, Dewhirst MW. Targeting lactate-fueled respiration selectively kills hypoxic tumor cells in mice. J Clin Invest. 2008;118(12):3930-3942. [CrossRef]
- de Baaij JHF, Hoenderop JGJ, Bindels RJM. Magnesium in man: implications for health and disease. Physiol Rev. 2015;95(1):1-46. [CrossRef]
- 38.Ohsumi Y. Historical landmarks of autophagy research. Cell Res. 2014;24(1):9-23. [CrossRef]
- 39.Youle RJ, Narendra DP. Mechanisms of mitophagy. Nat Rev Mol Cell Biol. 2011;12(1):9-14. [CrossRef]
- 40.Hardie DG, Ross FA, Hawley SA. AMPK: a nutrient and energy sensor that maintains energy homeostasis. Nat Rev Mol Cell Biol. 2012;13(4):251-262. [CrossRef]
- 41.Campisi J. Aging, cellular senescence, and cancer. Annu Rev Physiol. 2013;75:685-705. [CrossRef]
- 42.Youm YH, Nguyen KY, Grant RW, Goldberg EL, Bodogai M, Kim D, D’Agostino D, Planavsky N, Lupfer C, Kanneganti TD, Kang S, Horvath TL, Fahmy TM, Crawford PA, Biragyn A, Alnemri E, Dixit VD. The ketone metabolite β-hydroxybutyrate blocks NLRP3 inflammasome-mediated inflammatory disease. Nat Med. 2015;21(3):263-269. [CrossRef]
- 43.Saha T, Dash C, Jayabalan R, Khiste S, Kulkarni A, Kurmi K, Mondal J, Majumder PK, Bardia A, Jang HL, Sengupta S. Intercellular nanotubes mediate mitochondrial trafficking between cancer and immune cells. Nat Nanotechnol. 2022;17(1):98-106. [CrossRef]
- 44.Camacho-Pereira J, Tarragó MG, Chini CCS, Nin V, Escande C, Warner GM, Puranik AS, Schoon RA, Reid JM, Galina A, Chini EN. CD38 dictates age-related NAD decline and mitochondrial dysfunction through an SIRT3-dependent mechanism. Cell Metab. 2016;23(6):1127-1139. [CrossRef]
- 45.Moser CC, Keske JM, Warncke K, Farid RS, Dutton PL. Nature of biological electron transfer. Nature. 1992;355(6363):796-802. [CrossRef]
- 46.Marcus RA, Sutin N. Electron transfers in chemistry and biology. Biochim Biophys Acta. 1985;811(3):265-322. [CrossRef]
- 47.Chouchani ET, Pell VR, Gaude E, Aksentijević D, Sundier SY, Robb EL, et al. Ischaemic accumulation of succinate controls reperfusion injury through mitochondrial ROS. Nature. 2014;515(7527):431-435. [CrossRef]
- 48.Scialò F, Fernández-Ayala DJ, Sanz A. Role of mitochondrial reverse electron transport in ROS signaling: potential roles in health and disease. Front Physiol. 2017;8:428. [CrossRef]
- 49.Summerhayes IC, Lampidis TJ, Bernal SD, Nadakavukaren JJ, Nadakavukaren KK, Shepherd EL, et al. Unusual retention of rhodamine 123 by mitochondria in muscle and carcinoma cells. Proc Natl Acad Sci U S A. 1982;79(17):5292-5296. [CrossRef]
- 50.Chen LB. Mitochondrial membrane potential in living cells. Annu Rev Cell Biol. 1988;4:155-181. [CrossRef]
- 51.Modica-Napolitano JS, Aprille JR. Delocalized lipophilic cations selectively target the mitochondria of carcinoma cells. Adv Drug Deliv Rev. 2001;49(1-2):63-70. [CrossRef]
- 52.Zhao Y, Hu Q, Cheng F, Su N, Wang A, Zou Y, et al. SoNar, a highly responsive NAD+/NADH sensor, allows high-throughput metabolic screening of anti-tumor agents. Cell Metab. 2015;21(5):777-789. [CrossRef]
- 53.Bruzzone S, Guida L, Zocchi E, Franco L, De Flora A. Connexin 43 hemichannels mediate Ca2+-regulated transmembrane NAD+ fluxes in intact cells. FASEB J. 2001;15(1):10-12. [CrossRef]
- 54.Go S, Kramer TT, Verhoeven AJ, Oude Elferink RPJ, Chang JC. The extracellular lactate-to-pyruvate ratio modulates the sensitivity to oxidative stress-induced apoptosis via the cytosolic NADH/NAD+ redox state. Apoptosis. 2021;26(1-2):38-51. [CrossRef]
- 55.Williamson JR, Chang K, Frangos M, Hasan KS, Ido Y, Kawamura T, et al. Hyperglycemic pseudohypoxia and diabetic complications. Diabetes. 1993;42(6):801-813. [CrossRef]
- 56.Yap TA, Daver N, Mahendra M, Zhang J, Kamiya-Matsuoka C, Meric-Bernstam F, et al. Complex I inhibitor of oxidative phosphorylation in advanced solid tumors and acute myeloid leukemia: phase I trials. Nat Med. 2023;29(1):115-126. [CrossRef]
- 57.Jin C, Zeng S, Wu H, Hu X. Intracellular lactic acidosis reprograms glycolysis and mitochondrial anaplerosis in cancer cells. J Biol Chem. 2026;302(7):113150. [CrossRef]
- 58.Blaszczak W, Williams H, Swietach P. Autoregulation of H+/lactate efflux prevents monocarboxylate transport (MCT) inhibitors from reducing glycolytic lactic acid production. Br J Cancer. 2022;127(7):1365-1377. [CrossRef]
- 59.Kuiper C, Molenaar IGM, Dachs GU, Currie MJ, Sykes PH, Vissers MCM. Low ascorbate levels are associated with increased hypoxia-inducible factor-1 activity and an aggressive tumor phenotype in endometrial cancer. Cancer Res. 2010;70(14):5749-5758. [CrossRef]
- 60.Kuiper C, Dachs GU, Munn D, Currie MJ, Robinson BA, Pearson JF, et al. Increased tumor ascorbate is associated with extended disease-free survival and decreased hypoxia-inducible factor-1 activation in human colorectal cancer. Front Oncol. 2014;4:10. [CrossRef]
- 61.Kuiper C, Vissers MCM, Hicks KO. Pharmacokinetic modeling of ascorbate diffusion through normal and tumor tissue. Free Radic Biol Med. 2014;77:340-352. [CrossRef]
- 62.Asard H, Barbaro R, Trost P, Bérczi A. Cytochromes b561: ascorbate-mediated trans-membrane electron transport. Antioxid Redox Signal. 2013;19(9):1026-1035. [CrossRef]
- 63.Rolfe DF, Brand MD. Contribution of mitochondrial proton leak to skeletal muscle respiration and to standard metabolic rate. Am J Physiol. 1996;271(4 Pt 1):C1380-C1389. [CrossRef]
- 64.Divakaruni AS, Brand MD. The regulation and physiology of mitochondrial proton leak. Physiology (Bethesda). 2011;26(3):192-205. [CrossRef]
- 65.Nicholls DG. The non-ohmic proton leak—25 years on. Biosci Rep. 1997;17(3):251-257. [CrossRef]
- 66.Miwa S, Brand MD. Mitochondrial matrix reactive oxygen species production is very sensitive to mild uncoupling. Biochem Soc Trans. 2003;31(Pt 6):1300-1301. [CrossRef]
- 67.Echtay KS, Roussel D, St-Pierre J, Jekabsons MB, Cadenas S, Stuart JA, Harper JA, Roebuck SJ, Morrison A, Pickering S, Clapham JC, Brand MD. Superoxide activates mitochondrial uncoupling proteins. Nature. 2002;415(6867):96-99. [CrossRef]
- 68.Parker N, Vidal-Puig A, Brand MD. Stimulation of mitochondrial proton conductance by hydroxynonenal requires a high membrane potential. Biosci Rep. 2008;28(2):83-88. [CrossRef]
- 69.Zhang CY, Parton LE, Ye CP, Krauss S, Shen R, Lin CT, Porco JA Jr, Lowell BB. Genipin inhibits UCP2-mediated proton leak and acutely reverses obesity- and high glucose-induced beta cell dysfunction in isolated pancreatic islets. Cell Metab. 2006;3(6):417-427. [CrossRef]
- 70.Pons DG, Nadal-Serrano M, Torrens-Mas M, Valle A, Oliver J, Roca P. UCP2 inhibition sensitizes breast cancer cells to therapeutic agents by increasing oxidative stress. Free Radic Biol Med. 2015;86:67-77. [CrossRef]
- 71.Vozza A, Parisi G, De Leonardis F, Lasorsa FM, Castegna A, Amorese D, Marmo R, Calcagnile VM, Palmieri L, Ricquier D, et al. UCP2 transports C4 metabolites out of mitochondria, regulating glucose and glutamine oxidation. Proc Natl Acad Sci U S A. 2014;111(3):960-965. [CrossRef]
- 72.Derdak Z, Mark NM, Beldi G, Robson SC, Wands JR, Baffy G. The mitochondrial uncoupling protein-2 promotes chemoresistance in cancer cells. Cancer Res. 2008;68(8):2813-2819. [CrossRef]
- 73.Baffy G, Derdak Z, Robson SC. Mitochondrial recoupling: a novel therapeutic strategy for cancer? Br J Cancer. 2011;105(4):469-474. [CrossRef]
- 74.Tretter L, Adam-Vizi V. Uncoupling is without an effect on the production of reactive oxygen species by in situ synaptic mitochondria. J Neurochem. 2007;103(5):1864-1871. [CrossRef]
- 75.Angelini G, Gardella S, Ardy M, Ciriolo MR, Filomeni G, Di Trapani G, Clarke F, Sitia R, Rubartelli A. Antigen-presenting dendritic cells provide the reducing extracellular microenvironment required for T lymphocyte activation. Proc Natl Acad Sci U S A. 2002;99(3):1491-1496.
- 76.Srivastava MK, Sinha P, Clements VK, Rodriguez P, Ostrand-Rosenberg S. Myeloid-derived suppressor cells inhibit T-cell activation by depleting cystine and cysteine. Cancer Res. 2010;70(1):68-77. [CrossRef]
- 77.Yan Z, Garg SK, Banerjee R. Regulatory T cells interfere with glutathione metabolism in dendritic cells and T cells. J Biol Chem. 2010;285(53):41525-41532. [CrossRef]
- 78.Birsoy K, Wang T, Chen WW, Freinkman E, Abu-Remaileh M, Sabatini DM. An essential role of the mitochondrial electron transport chain in cell proliferation is to enable aspartate synthesis. Cell. 2015;162(3):540-551. [CrossRef]
- 79.Sullivan LB, Gui DY, Hosios AM, Bush LN, Freinkman E, Vander Heiden MG. Supporting aspartate biosynthesis is an essential function of respiration in proliferating cells. Cell. 2015;162(3):552-563. [CrossRef]
- 80.Titov DV, Cracan V, Goodman RP, Peng J, Grabarek Z, Mootha VK. Complementation of mitochondrial electron transport chain by manipulation of the NAD+/NADH ratio. Science. 2016;352(6282):231-235. [CrossRef]
- 81.Cracan V, Titov DV, Shen H, Grabarek Z, Mootha VK. A genetically encoded tool for manipulation of NADP+/NADPH in living cells. Nat Chem Biol. 2017;13(10):1088-1095. [CrossRef]
- 82.Luengo A, Li Z, Gui DY, Sullivan LB, Zagorulya M, Do BT, Ferreira R, Naamati A, Ali A, Lewis CA, Thomas CJ, Spranger S, Matheson NJ, Vander Heiden MG. Increased demand for NAD+ relative to ATP drives aerobic glycolysis. Mol Cell. 2021;81(4):691-707.e6. [CrossRef]
- 83.Chen Q, Espey MG, Krishna MC, Mitchell JB, Corpe CP, Buettner GR, Shacter E, Levine M. Pharmacologic ascorbic acid concentrations selectively kill cancer cells: action as a pro-drug to deliver hydrogen peroxide to tissues. Proc Natl Acad Sci U S A. 2005;102(38):13604-13609. [CrossRef]
- 84.Chen Q, Espey MG, Sun AY, Pooput C, Kirk KL, Krishna MC, Khosh DB, Drisko J, Levine M. Ascorbate in pharmacologic concentrations selectively generates ascorbate radical and hydrogen peroxide in extracellular fluid in vivo. Proc Natl Acad Sci U S A. 2007;104(21):8749-8754. [CrossRef]
- 85.Buettner GR. The pecking order of free radicals and antioxidants: lipid peroxidation, alpha-tocopherol, and ascorbate. Arch Biochem Biophys. 1993;300(2):535-543. [CrossRef]
- 86.Wu H, Ying M, Hu X. Lactic acidosis switches cancer cells from aerobic glycolysis back to dominant oxidative phosphorylation. Oncotarget. 2016;7(26):40621-40629. [CrossRef]
- 87.Zhang J, Wang YT, Miller JH, Day MM, Munger JC, Brookes PS. Accumulation of succinate in cardiac ischemia primarily occurs via canonical Krebs cycle activity. Cell Rep. 2018;23(9):2617-2628. [CrossRef]
- 88.Chinopoulos C. Succinate in ischemia: where does it come from? Int J Biochem Cell Biol. 2019;115:105580. [CrossRef]
- 89.Birkmayer W, Birkmayer GJD, Vrecko K, Mlekusch W. The coenzyme nicotinamide adenine dinucleotide (NADH) improves the disability of parkinsonian patients. J Neural Transm Park Dis Dement Sect. 1989;1(4):297-302. [CrossRef]
- 90.Libiad M, Vitvitsky V, Bostelaar T, Bak DW, Lee HJ, Sakamoto N, Fearon E, Lyssiotis CA, Weerapana E, Banerjee R. Hydrogen sulfide perturbs mitochondrial bioenergetics and triggers metabolic reprogramming in colon cells. J Biol Chem. 2019;294(32):12077-12090. PMID: 31213529. [CrossRef]
- 91.Vitvitsky V, Kumar R, Libiad M, Maebius A, Landry AP, Banerjee R. The mitochondrial NADH pool is involved in hydrogen sulfide signaling and stimulation of aerobic glycolysis. J Biol Chem. 2021;296:100736. PMID: 33933447. [CrossRef]
- 92.Carballal S, Vitvitsky V, Kumar R, Hanna DA, Libiad M, Gupta A, Jones JW, Banerjee R. Hydrogen sulfide stimulates lipid biogenesis from glutamine that is dependent on the mitochondrial NAD(P)H pool. J Biol Chem. 2021;297(2):100950. PMID: 34252456. [CrossRef]
- 93.Cooper CE, Brown GC. The inhibition of mitochondrial cytochrome oxidase by the gases carbon monoxide, nitric oxide, hydrogen cyanide and hydrogen sulfide: chemical mechanism and physiological significance. J Bioenerg Biomembr. 2008;40(5):533-539. [CrossRef]
- 94.Hanna DA, Chen B, Shah YM, Khalimonchuk O, Cunniff B, Banerjee R. H2S remodels mitochondrial ultrastructure and destabilizes respiratory supercomplexes. J Biol Chem. 2025;301:108433. [CrossRef]
- 95.Borisov VB, Forte E. Impact of hydrogen sulfide on mitochondrial and bacterial bioenergetics. Int J Mol Sci. 2021;22(23):12688. [CrossRef]
Figure 2.
Cyclic reductive impulse: differential response healthy vs cancer cell.
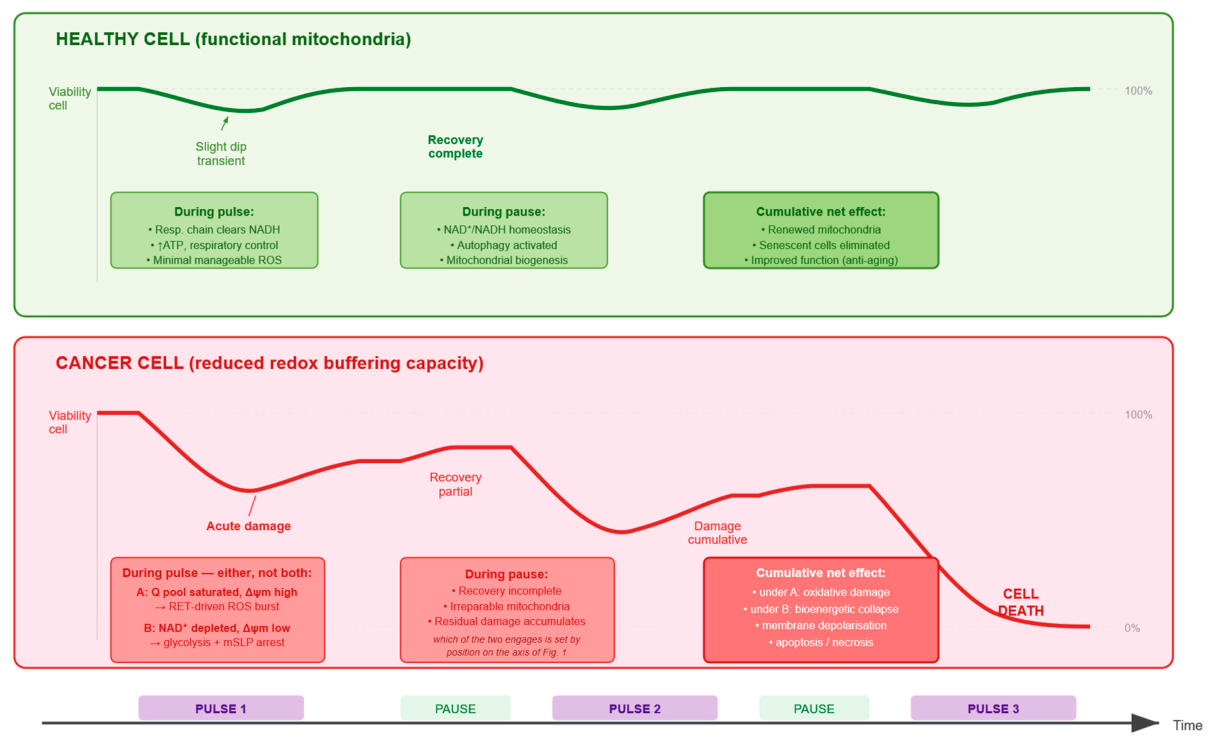
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.