

Submitted:
18 September 2026
Posted:
18 September 2026
You are already at the latest version
Abstract
Background: Work-related Musculoskeletal Disorders (WMSDs) are a prevalent issue in wall construction tasks due to repetitive movement and awkward postures. The current study aimed to evaluate the postural risks and joint reaction forces (JRFs) of the shoulder, elbow, and neck joints during wall construction tasks performed at 0 cm (foot) and 77 cm working heights. Methods: Twelve male students (age: 21.83±1.27 years) performed four simulated construction tasks. Actual body movement data were captured with Inertial Measurement Unit (IMU) sensors and processed in the AnyBody Modeling System via a 3D musculoskeletal (MSK) model. The Rapid Upper Limb Assessment (RULA) method was used to evaluate the postural risk level. The joint reaction forces were calculated by inverse dynamics simulation and analyzed using a two-way ANOVA. Results: Working at 0 cm height resulted in high RULA scores of 7 (very high risk) during mortar scooping and picking up the brick. Working at 77 cm height, all tasks had modal and median RULA scores of 4, indicating lower postural risk. ANOVA results showed highly significant main and interaction effects of working height and tasks on shoulder, elbow, and neck JRFs (all p<0.001). Height exhibited exceptionally large effect sizes on shoulder (partial η² = 0.98), and elbow (partial η² = 0.92) joints. Conclusions: Therefore, a working height approximately midway between the worker's knee and waist heights (averaging 77 cm) effectively minimizes both postural risk and biomechanical joint loading during wall construction tasks.
Keywords:
work-related musculoskeletal disorders (WMSDs)
; joint reaction force (JRF)
; musculoskeletal (MSK) modeling
; rapid upper limb assessment (RULA)
; wall construction tasks
1. Introduction
Wall construction tasks are associated with various intensive body movements. Due to the inherent characteristics of these tasks, workers frequently engage in repetitive movements and awkward body postures. These movements can result in potential work-related musculoskeletal disorders (WMSDs) including illnesses or injuries in the various anatomical structures such as joints, muscles, and ligaments [1]. These injuries not only impact workers’ physical health but also affect production and economic growth [2]. Thus, it is necessary to observe workers’ postural risks and joint reaction forces that contribute to WMSDs in order to protect worker health and enhance economic interest. In addition, a proper postural risk assessment method is essential to mitigate WMSD problems.
Various observation methods, including Rapid Upper Limb Assessment (RULA) [3], Rapid Entire Body Assessment (REBA) [4], Ovako Working Posture Analyzing System (OWAS) [5], and Novel Ergonomic Postural Assessment (NERPA) [6], have been widely applied to evaluate ergonomics risks associated with WMSDs in occupational settings. Among these methods, the RULA is the most frequently used because it provides a rapid assessment of upper-limb postural risk. Previous studies have successfully applied RULA and its modified versions to identify awkward postures and evaluate ergonomics risks in construction and industrial tasks, where excessive trunk bending, lifting, and pulling are associated with WMSD risk [7,8,9,10]. However, these studies mainly rely on manual observation or video-based posture scoring, which are subjective, time-consuming, and dependent on the evaluator’s judgment. In addition, although these approaches can easily assess postural risk level, they fail to quantify the biomechanical loading experienced by the joints during task performance. Consequently, the relationship between observational postural risk scores and objective biomechanical measures, such as joint reaction forces, remains insufficiently understood, particularly for wall construction tasks. Addressing this gap requires integrating objective motion-capture data with musculoskeletal modeling to evaluate both postural risk and biomechanical loading.
With the prompt advancement of optical vision technology, investigators have utilized it to estimate human posture risk using 2D images from cameras. In this vision-based technology, 2D images are used to classify critical postures without any additional operations [11]. Postural risk assessment rules are then applied to evaluate the risk of WMSDs. Currently, this approach is widely used in human-machine based risk assessment in office environment [12] and material handling [13] sectors. However, these vision-based methods may overlook certain working postures, such as twisting movements. In addition, although widely utilized, the outcomes of vision-based methods are often deemed subjective and inadequate for supporting biomechanical analysis [14]. Researchers in India [15], Malaysia [16], and Saudi Arabia [17] evaluated the prevalence of WMSD risk among construction workers and found that the occurrence rates of WMSDs in construction tasks were very high, at 84%, 66.7%, and 50% respectively. Despite high reported prevalence of WMSDs risks among construction workers, few studies have objectively evaluated the postural and biomechanical risk factors associated with wall construction tasks. To assess the risk of WMSDs, the majority of researchers have used survey methods based on questionnaires. However, these survey-based methods are not capable of evaluating the postural and biomechanical risks associated with WMSDs. Therefore, objective assessment through motion capture and musculoskeletal modeling is needed to better understand the biomechanical mechanisms underlying WMSDs risk. In addition, various biomechanical factors, including awkward working postures [18], bending and twisting postures [19], joint reaction forces and muscle activity [20] have been associated with WMSD risk among construction workers. Researchers have developed a 3D dynamic model to evaluate spinal stress during manual material handling tasks based on body mass [21]. They found that the joint reaction forces in the lower back are influenced by back bending and twisting angles.
Therefore, the aim of the current study was to evaluate the postural risk levels and their association with the joint reaction forces of the shoulder, elbow, and neck joints during wall construction tasks performed at foot (0 cm) and 77 cm working heights. The 77 cm height was chosen because it corresponds to the average of the participants’ knee and waist heights, representing an intermediate and ergonomically comfortable working level. For this purpose, the authors investigated the postural risk using actual body movements, and joint kinematics were analyzed based on task video recordings and IMU sensor data. This study also quantified joint reaction forces in the shoulder, elbow, and neck joints using a three-dimensional musculoskeletal (MSK) model to evaluate biomechanical loading.
2. Materials and Methods
2.1. Participants
A total of twelve male university students (age: 21.83 ± 1.27 years; height: 172.03 ± 5.92 cm; and weight: 64.48 ± 9.85 kg) participated in this study. Details of participant information are shown in Table 1. This sample size was chosen for this laboratory-based biomechanical study, where each participant performed all experiments using a repeated-measures design. Healthy university students were recruited to control variability associated with construction experience, physical capacity, and work techniques, allowing for a controlled evaluation of the effects of working height on postural risk and joint reaction forces. However, the findings do not directly represent professional construction workers.
All participants in the experiment participated voluntarily and ensured they had no physical discomfort. Prior to the experiment, participants provided personal information and informed consent in accordance with the ethical approval (No. 2023-8) from the Kanazawa University Ethics Committee, Japan.
2.2. Experimental Condition and Procedures
An imitation of the wall construction task was constructed in a laboratory environment (Figure 1). During the experiment, participants performed four tasks at two working heights: foot level (0 cm) and 77 cm. The 77 cm working height was chosen because it falls midway between the average knee height (47 cm) and waist height (107 cm) of the participants. This intermediate height was chosen to represent a practical working level that minimizes excessive trunk flexion while remaining below waist level. Studies [22,23] have shown that work done between knee and waist height reduces postural loading and musculoskeletal stress compared to floor-level tasks, making it suitable for assessing biomechanical risks during wall construction.
At foot level height (where the working surface for mortar and bricks was 0 cm), participants were instructed to carry out the following tasks: scooping mortar from foot level (task-1), applying mortar to foot level (task-2), picking up a brick from foot level (task-3), and laying a brick on foot level (task-4). At 77 cm level working height, where the working surface for mortar and bricks was 77 cm, the participants were asked to perform the same four tasks. The tasks 1 and 2 were performed using the right hand, while tasks 3 and 4 were performed using the left hand. Participants repeated each task three times; data from correctly executed trials were selected for analysis. The actual weight of the brick was 2.5 kg, while the trowel with mortar was 0.6 kg.
2.3. Data Collection Procedures
Simulated task movements of wall construction were captured using two motion capture systems. In the experiments, 17 Inertial Measurement Unit (IMU) sensors (Perception Neuron Studio, Noitom Ltd., China) were used to capture three-dimensional (3D) body movement at a sampling frequency of 100 Hz. IMU sensors, consisting of tri-axial accelerometers, gyroscopes, and a magnetometer, were attached to participants’ bodies according to the manufacturer’s recommended full-body configuration [24]. As the manufacturer does not disclose the mathematical implementation of the sensor fusion algorithm, the internal fusion algorithm was not modified. Before each trial, the IMU sensors were calibrated using the manufacturer’s procedure, a standard static T-pose, to establish sensor-to-body alignment. The calibrated body motions were visually compared with the synchronized video recordings to verify consistency between the measured and simulated task movement. These preprocessing procedures were applied to minimize the influence of sensor noise and drift on the estimated joint reaction forces.
These IMU sensors are less expensive, easy to use and portable, and no marker is required like other optical base motion capture systems [25]. Previous studies have evaluated the validity of the Perception Neuron system for full-body and upper-body human motion capture [25,26]. However, these validation studies were not conducted specifically for construction tasks. Therefore, in the current study, IMU sensors were used to capture three-dimensional body movements during simulated wall construction tasks. In addition, a video camera (Clear One Inc.) was used to directly observe the actual work movements. The video data was captured at 30 frames per second (fps).
2.4. Joint Kinematics and Angle Assessment
Body joint angles are essential for analyzing the postural risk levels. Although the motion -capture system provides three-dimensional body-motion data, the raw IMU output does not provide the anatomical joint angles and musculoskeletal quantities required for the current analysis. Therefore, the IMU data were processed within a musculoskeletal (MSK) model using the AnyBody Modeling System Software version 7.4 (AnyBody Technology A/S, Aalborg, Denmark), to derive the joint kinematics required for postural risk assessment and subsequent biomechanical analysis. The AnyBody Modeling System is a cost-effective tool for musculoskeletal simulation; however, it requires correct motion capture data, participant-specific anthropometric data, and careful preprocessing to obtain dependable simulation outputs. In this study, these requirements were fulfilled by retrieving full-body motion data by 17 IMU sensors and participant-specific anthropometric data before performing inverse kinematic analysis [27]. In the present study, inverse kinematics simulation was performed using motion capture data to calculate the joint kinematics. The resulting joint kinematic outputs included the angular motion of the upper arm, lower arm, wrist, neck, and trunk. Outcome variables for postural assessment included the joint angles of the upper arm, lower arm, wrist, neck, and trunk. Specifically, the flexion angles of the upper arm, lower arm, and trunk, and the extension angles of the wrist and neck were extracted from the inverse kinematics analysis. The peak joint angle over each task cycle was used for analysis. These joint angles were subsequently used to characterize the working postures and to determine postural risk scores.
Statistical analyses were performed to examine differences in postural risk level between the two working heights and across four wall construction tasks. The working heights (0 cm and 77 cm) and tasks (Tasks 1–4) were considered the comparison factors. The outcome variables for postural analysis were RULA score and joint angles of the upper arm, lower arm, wrist, neck, and trunk.
2.5. Postural Risk Analysis
The Rapid Upper Limb Assessment (RULA) method was applied to assess the risk of selected postures in wall construction tasks. RULA is an economical and realistic method for assessing upper-limb ergonomic risks compared to other observational methods [3]. The acquired RULA value was scored based on Figure 2 [28]. Table 2 shows the postural risk and required activity levels. Under the RULA technique, body parts are categorized into two groups, namely Group A, comprising the upper arm, lower arm, and wrist, and Group B, comprising the neck, trunk, and legs. When assessing the body parts, a muscle use adjustment factor score of 0 or 1 and a force/load adjustment score of 0 to 3 are summed up with the corresponding group score (A and B), according to the RULA technique. Finally, the RULA score is derived from the RULA scoring tables, ranging between 1 and 7, where higher scores indicate greater postural risk and a greater need for ergonomic intervention.
2.6. Joint Reaction Force Assessment Using Inverse Dynamics
The participant-specific MSK model was generated using each participant’s height and body weight; however, this approach provides an approximate representation of individual anthropometry and does not account for inter-individual differences in segment lengths, joint center location or muscle attachment geometries. Therefore, the estimated muscle moment arms and joint reaction forces may contain scaling-related uncertainties.
The MSK model is constructed from rigid segments, such as bones, linked by joints, including revolute and ball-and-socket configurations, that define its degrees of freedom (DOF) and are routed with muscles. To represent subject-specific anthropometrics, standard repository models are rescaled using parameters like height, weight, and segment lengths. The model incorporates realistic external loading conditions by accounting for gravitational forces, segment masses, and ground reaction forces. Motion capture kinematics and external force data are evaluated via inverse dynamics to estimate internal biomechanical loads, such as muscle forces and joint reaction forces. Because the underlying mechanical equations are indeterminate, a polynomial muscle recruitment optimization algorithm is applied to determine muscle load sharing [29]. In this study, inverse dynamics simulations were executed in the validated [30,31] AnyBody Modeling System using its standard equilibrium equations and muscle recruitment criterion (Equation (1)) to derive joint reaction forces [31].
Here, G represents the objective function; i denotes the number of muscles; N is the total number of muscles; Fi is the muscle force; Fi, max represents the maximum isometric muscle force; f is the vector of joint and muscle forces; C is the coefficients matrix; and r denotes a known vector of inertial and external forces.
The joint reaction forces were calculated separately for two working heights (0 cm and 77 cm) and for each of the four tasks. Because the participants used different hands for the tasks, the reaction forces of the corresponding working- side shoulder and elbow joints were evaluated as described in the Result section. The neck joint reaction force was evaluated for the C1-C0 joint. This joint was not represented as a direct clinical indicator of overall neck WMSD risk. The maximum joint reaction force during each normalized task cycle was subsequently used for comparison between the two working heights.
Statistical analyses were performed to examine differences in biomechanical measures between the two working heights and across the four wall construction tasks. The working heights (0 cm and 77 cm) and tasks (Tasks 1–4) were considered the comparison factors. For biomechanical analysis, the outcome variables were the maximum joint reaction forces of the shoulder, elbow, and neck joints. Because the same participants performed all tasks at both working heights, comparisons were conducted using within-subject data
To reduce high-frequency measurement noise, the motion trajectories were processed using a fourth-order low-pass Butterworth filter with a cutoff frequency of 6 Hz prior to running inverse dynamics simulations.
2.7. Statistical Analysis
The normality of the data was checked by the Shapiro-Wilk test. A two-way analysis of variance (ANOVA) test was conducted to evaluate the main effects of working height and tasks as well as their interaction effect, on selected joint reaction forces. Statistical analyses were conducted by the Statistical Package for the Social Sciences version 27.0 (IBM, USA). Statistical significance was set at p <0.05, with partial eta square (η²) reported as a measure of effect size.
3. Results
3.1. Postural Risk Analysis
The actual body movements and 3D estimated postures of the selected experimental tasks performed at foot level height are shown in Figure 3. Table 3 presents the RULA scores, and associated risk levels of subjects in four stages of the selected four tasks at 0 cm height. The RULA scores were estimated for each participant (n = 12) across four tasks and two working heights. To summarize group-level postural risk, the mode and median of the individual scores were calculated. In addition, the percentage distribution of participants across each RULA risk category (Negligible, Low, Medium, High/Very High) was reported for each task condition. The posture evaluation results (Table 3) indicate that participants assumed awkward postures due to the large angles of the upper arm, lower arm, neck, and trunk for all tasks.
At foot level height, while the worker scooped the mortar (task-1) and picked up the brick (task-3), resulting in RULA scores of 7, with 100 % of observed participants falling into the high-risk level category, indicating that immediate corrective action is required. In contrast, tasks 2 and 4 resulted in RULA scores of 6, which corresponded to a medium risk, observed in 83.3% and 91.7% of subjects respectively. Therefore, further investigation and changes should be implemented soon. These classifications were based on the RULA score to risk correspondence presented in Table 2. In addition, higher joint angles for the trunk, upper arm, neck, and lower arm indicate the highest risk of WMSDs for task 1 and 3. Hence, it is essential to promptly modify the existing postures, and corrective actions for improvement are required immediately.
In addition, the participants also performed the same four tasks at 77 cm working height (average height of knee and waist), as shown in Figure 4. Working at 77 cm height, the participants had to bend and twist less compared to foot height throughout tasks 1 to 4, resulting in all four tasks having a median and modal RULA score of 4, indicating normally low postural risk (Table 4). This RULA score corresponds to a low-risk level according to the RULA classification. Here the task -2 had the highest risk, 91.7% of the participants scoring 4 and 8.3% scoring 5 (medium risk). In contrast, the other three tasks showed 100% low risk (score 3-4). However, the upper arm also showed greater flexion (65.30° ± 6.1°) compared to other body parts (i.e., trunk, neck, and wrists). Therefore, investigations into changing body postures with different workstations may be needed in the future. Meanwhile, the forthcoming text will examine the biomechanical load in terms of the risk of joint reaction forces occurring in the shoulder, elbow, and neck joints.
3.2. Joint Reaction Force Analysis
The joint reaction force (JRF) is considered as a biomechanical risk factor for developing WMSDs. Therefore, this study focused the joint reaction force on the shoulder, elbow, and neck joints. These joints were selected because they represent the main proximal upper-limb and neck regions included in the reaching and upper limb movements to perform the wall construction tasks. The wrist and trunk were excluded in this study because the current analysis was designed to focus on the upper-limb biomechanical loading. In contrast, the trunk and wrist postures were considered in the postural risk assessment. This selection defines the limitation of the present biomechanical analysis and does not imply that the wrist and trunk are unimportant contributors to musculoskeletal loading for construction workers. The joint reaction forces of the shoulder, elbow, and neck actively performing each task were measured throughout the simulated tasks by running inverse dynamics simulations. The maximum JRF for each task cycle was calculated and the maximum JRFs of all participants for each task were averaged. Figure 5 represents the joint reaction forces (JRFs) of the shoulder, elbow, and neck, normalized to body weight (%BW), at 0 cm and 77 cm working heights across four construction tasks. Due to experimental requirements, participants used the right hand for Tasks 1 and 2 (mortar scoping and placing) and the left hand for Tasks 3 and 4 (brick picking and laying), the corresponding shoulder and elbow joints of the working arm were analyzed for each task. The reaction force of C1-C0 joint was measured to address the neck joint across all tasks. Overall, the shoulder joint experienced the greatest reaction forces across all tasks and working heights, meanwhile the elbow and neck showed comparatively lower forces.
The shoulder JRF was constantly higher at 0 cm than at 77 cm for all four tasks. The greatest shoulder JRF was found during Task 2 at 0 cm (approximately 38% BW), followed by Task 1 (approximately 37% BW) and Task 3 (approximately 34% BW). Raising the working height from 0 cm to 77 cm reduced the shoulder JRF to approximately 19–29% BW, indicating that the higher working position generally minimizes loading on the shoulder. This pattern is consistent with the higher trunk and upper-limb flexion required when working at the lower height.
The elbow JRFs were substantially lower than the shoulder JRFs, generally ranging from approximately 5–13% BW. At 77 cm working height, remarkable changes in elbow JRF were observed in Tasks 1, 2, and 4, whereas Task 3 showed a comparatively small change. Similarly, the neck JRF generally reduced or remained almost the same at the 77 cm working height, with the highest neck JRF found during Task 2 at both working heights. These findings suggest that increasing the working height from 0 cm to 77 cm can minimize the mechanical loading experienced by several upper-body joints.
Table 5 represents the mean joint reaction forces (JRF) for the shoulder, elbow, and neck across four tasks at two selected working heights (0 cm and 77 cm). Overall, upper-body biomechanical loading was mainly dominated by shoulder JRF, followed by neck and elbow forces across almost all conditions. Raising the working height from 0 cm to 77 cm resulted in a remarkable reduction in shoulder JRF across all evaluated tasks. The most substantial reduction was observed in Task 2, where mean shoulder JRF decreased by around 48.5% (from 233.00 ± 4.26 N to 119.87 ± 0.76 N). Task 1 and Task 4 showed similar descending trends, decreasing by 24.86% (from 233.82 ± 9.41 N to 175.70 ± 2.14 N) and 21.40% (from 168.00 ± 1.85 N to 132.05 ± 1.10 N), respectively. Task 3 showed the minimal reduction in shoulder loading of 14.27% (from 211.80 ± 1.88 N to 181.57 ± 1.58 N). The orderly reduction in the JRFs at the elevation suggests that adjusting the working position closer to functional waist height effectively reduces moment arms around upper extremity joints. These findings indicate elevated task positioning as a viable intervention strategy to mitigate postural stress and reduce the risk of WMSDs in manual wall construction tasks.
Table 6 represents the results of a two-way ANOVA evaluating the effects of working heights (0 cm vs. 77 cm) and task type (Task 1 to Task 4) on joint reaction forces (JRF) at the shoulder, elbow and neck. The ANOVA analysis showed significant main effects for both working height and task type, as well as significant interaction effect (working height × task), across all three joint regions (all p <0.001). For shoulder JRF, working height (F = 6442.38, partial η² = 0.98), task (F = 742.85, partial η² = 0.96), and their interaction (F = 589.65, partial η² = 0.95) all demonstrated statistically significant effects. Likewise, significant main and interaction effects were observed for elbow JRF, with partial η² values ranging from 0.90 to 0.95. For neck JRF, task types exhibited the largest effect (F = 2343.60, partial η² = 0.99), followed by working height (F = 150.51, partial η² = 0.63), whereas the interaction effect was comparatively lower but remained statistically significant (partial η² = 0.40). These findings demonstrate that the biomechanical load (i.e., joint reaction forces) associated with specific construction tasks is strongly dependent on working height.
4. Discussion
The present study used an IMU sensors-based data collection method to evaluate the postural risk and assess the related WMSD risk based on joint reaction force as a parameter of biomechanical analysis more accurately. For this purpose, critical body postures were first identified through video data. The authors then evaluated the postural risk based on kinematics data from IMU sensors. Furthermore, the joint reaction forces in different upper body joints as risk factors for WMSDs were assessed by using a 3D MSK model.
Workers engage in wall construction activities that involve various awkward working postures, such as scooping and laying mortar, as well as picking up and placing bricks into position. From the posture assessment, the authors found that in tasks 1 and 3, scooping and picking up bricks using the arms, and the trunk are more responsible for developing WMSDs compared to tasks 2 and 4 as shown in Table 3. The possible reasons for this can be attributed to awkward postures involving high upper arm flexion (task-1: 54.22° ± 6.1°, task-3: 78.97° ± 7.2°) and high trunk bending angles (task-1: 40.69° ± 4.8°, task-3: 45.28° ± 4.9°). Repetitive and prolonged adoption of these awkward working postures can increase the risk of WMSDs or, in the worst-case scenario, lead to accidents and loss of efficiency, as supported by Mallapiang et al. [32]. Kulkarni et al. [33] found such a type of problem among material transportation and plastering workers. Rahman et al. investigated that bricklayer workers are at high risk in awkward body postures [34]. Therefore, the current working postures need further investigation, and modification must be applied to protect the workers and improve productivity.
In addition, a 77 cm brick wall was also made on the left side of the participant for placing mortar and laying bricks. This height corresponds to the average knee and waist level height of the participants. Posture assessment at 77 cm working height showed that the joint angles for the upper arm and trunk during tasks 1 and 3 were reduced but there was a significant change for the lower arm that leads to lower risk level as shown in Table 4. Working at 77 cm height, workers did not need to bend or twist their back during wall construction, which was the possible reason for lower joint angles during examined tasks. The lower RULA scores at 77 cm indicate that this working height may provide a more favorable posture than the foot-level condition. These findings indicate that working at 77 cm height from the surface can create comfortable workstations for workers and reduce the postural risk and associated risk of WMSDs.
In this study, the joint reaction forces of the elbow, shoulders, and neck were analyzed at foot level height and 77 cm height to understand the role of these forces in the development of WMSDs. The joint reaction forces refer to the forces that occur at the articulating surfaces of a joint in response to external loads or muscular contractions that can lead to WMSDs. From the joint reaction force analysis at foot level height (Table 5), the shoulder exhibited higher joint reaction forces compared to the elbow and neck. This finding can be attributed to participants moving their working arm to reach the workplace, which increased the shoulder arm angle. This movement increases the greater mechanical loading in the shoulder joint, leading to pain in the shoulder. Maciukiewicz et al. [35] and Skovlind et al. [36] reported similar findings among drilling workers and supermarket workers, respectively.
As shown in Figure 5, the shoulder joint exhibited the maximum reaction force among the selected upper-body joints across all tasks and working heights. Joint reaction forces were generally higher at the 0 cm working height than at 77 cm, particularly for the shoulder, with the highest shoulder loading observed during Task 2 at 0 cm (approximately 38% BW). That shoulder JRF remained high at the elevated working height, despite smaller shoulder flexion, can be explained by the external moment created by the load around the shoulder joint. When the arm stays straight the hand and load stay further from the shoulder joint, which makes the perpendicular moment arm of the load larger. As a result, the shoulder muscles must work harder to balance the moment and keep the arm in place which raises the shoulder joint reaction force. Therefore, shoulder joint reaction force should not be judged by how much the shoulder is bent; instead shoulder joint reaction force is influenced by where the load sits how the joint is set up and the lengths of the moment arms. This mechanical view explains why shoulder joint reaction force was higher, at the height where shoulder flexion was minimal. In addition, the longer lever arm increases the torque or rotational force acting on the joint, leading to higher joint reaction forces, as similarly reported by Borrelli et al. [37]. Increasing the working height from 0 cm to 77 cm resulted in an obvious reduction in shoulder JRF across all tasks, while elbow and neck JRFs also generally decreased or remained comparatively the same. This reduction in joint loading at the higher working height may be attributed to the more favorable working posture and reduced upper-body flexion required compared with working near floor level.
As shown in Table 5, the highest JRF was found in the shoulder, which was the primary biomechanical load across all conditions with a peaking at around 233 N during Task 1 and Task 2 at the 0 cm working height. It indicates that working height significantly influences upper-limb biomechanical load. The relatively higher shoulder joint reaction force at lower working heights may be related to changes in upper-limb configuration, including increased lower-arm bending, which can modify the external moment acting about the shoulder. However, this relationship should be interpreted cautiously because the present study did not directly quantify the contribution of individual joint kinematics to the shoulder reaction force. The marked reduction in shoulder joint reaction force at the 77 cm working height highlights the ergonomic advantage of optimizing workplace geometry. Performing tasks at ground level (0 cm) requires increased trunk flexion and extended arm reach, which lengthens the gravitational moment arms of the upper extremities and external loads relative to the shoulder complex. Raising the working surface to 77 cm reduces forward inclination and lever arm length, thereby decreasing the required muscle recruitment and compressive joint reaction forces at the shoulder.
Notably, while elevated working height universally alleviated shoulder load, its impact on the neck and elbow depended heavily on specific task demands. For instance, neck JRF remained high in Task 2 regardless of height (93.33 N at 0 cm vs. 91.00 N at 77 cm), suggesting that Task 2 involves sustained head flexion or visual alignment constraints that are not mitigated by surface height alone. Similarly, the dramatic drop in elbow load during Task 4 at 77 cm (23.18 N) indicates a shift toward a more neutral forearm posture when working at table height. These findings demonstrate that elevating working surfaces effectively reduces major shoulder load, but task-specific modifications are necessary to address residual neck and distal limb stresses. This is consistent with past biomechanical studies regarding upper extremity stress during low-elevation manual operations [38,39]. Increasing the working height to 77 cm yields a noticeable decrease in joint reaction forces across all four tasks, most notably lightening shoulder load down to approximately 120 N in Task 2 and lowering Elbow JRF to below 25 N in Task 4. These graphical trends determine that optimizing working height toward functional waist level effectively lowers moment arms around the upper extremity joint. These findings support established ergonomic guidelines that recommend elevated task positioning to minimize WMSDs risk. This laboratory-based analysis suggests that a working height approximately midway between the knee and waist height of the worker may provide a more ergonomically favorable workstation. In the present study, this corresponded to an average working height of 77 cm among the participants. Working at 77 cm working height (i.e., intermediate working height between the knee and waist level) can strike a balance between postural and biomechanical risks.
Table 6 indicates that working height is significantly associated with shoulder, elbow, and neck JRFs, demonstrating large effect sizes (partial η² = 0.98, 0.92, and 0.63, respectively). This confirms that varying the working height significantly affects on the upper body mechanical load. Van der Molen et al. [40] reported that adjusting the working height during bricklaying helps to reduce prolonged trunk flexion and lower back discomfort, supporting the importance of the selection of suitable working positions for reducing biomechanical loads in construction work.
The significant main effect of tasks on shoulder, elbow, and neck JRFs (all p < 0.001; partial η² = 0.96–0.99) further indicates that biomechanical demands are strongly task dependent. The exceptionally large effect size for neck JRF (partial η² = 0.99) suggests that task-specific body posture and upper-body positioning play an important role in cervical loading during wall construction. This is supported with past study on construction sectors showing that different working sequences and body arm postures lead to distinct levels of upper-limb workload [41].
In addition, the interaction effect (working height × task) was statistically significant across all three joints (p < 0.001), showing large effect sizes for the shoulder (partial η² = 0.95) and elbow (partial η² = 0.90) and a moderate-to-large effect for the neck (partial η² = 0.40). This result indicates that the effect of working height was not the same for all tasks; rather, the change in upper-body loading associated with working height depended on the nature of the task. Previous study among masonry workers reported that the biomechanical workload differs considerably across the different working heights, working at knee-height associated with greater trunk flexion and work at or above shoulder level height associated with greater neck and shoulder muscular load [42]. Therefore, findings of the current study demonstrate the need to consider both working height and task characteristics when evaluating ergonomically appropriate working positions for wall construction.
However, this study has several limitations. First, the experiment was conducted under controlled laboratory setting using twelve healthy male university students rather than professional construction workers. Therefore, the generalizability of the findings to real construction sites should be interpreted with caution. Future studies should include larger and more diverse samples of professional and skilled construction workers and evaluate wall construction tasks under actual field conditions to further validate the present findings to confirm this more accurately.
Second, the subject-specific scaling of the MSK model was based primarily on body height and weight. Future studies should incorporate detailed segment-level anthropometric data, and where feasible, imaging-based anatomical information to improve subject-specific model scaling and biomechanical analysis. A third limitation is that cervical loading was evaluated only for the C1–C0 (atlanto-occipital) joint. Even though this evaluation shows a sign of upper cervical mechanical loading, it does not fully represent other lower cervical levels, such as C5–C7, which may be more relevant to neck problems. Future studies should include multi-level cervical joint loading to provide a more comprehensive assessment of neck musculoskeletal risk. Fourth, because the current study evaluated only the shoulder, elbow, and neck joint reaction forces, we recognize that lumbar loading (e.g., especially at L5/S1) is an important factor for the development of WMSDs in construction workers. Future studies should include lumbar spine reaction forces to highlight the biomechanical relevance of the findings. Fifth, because the current study estimated the joint reaction force using the AnyBody model software, the results were not cross-validated against experimental data such as EMG, force platforms or optical motion capture. Future studies should include such validation to enhance biomechanical accuracy.
In addition, future studies should integrate trunk (lumbar) joint and wrist joint reaction forces to provide a more comprehensive assessment of WMSDs risk during wall construction tasks.
5. Conclusions
The postural risk and joint reaction forces of the shoulder, elbow, and neck joints were evaluated as parameters of biomechanical load during wall construction tasks at foot (0 cm) and 77 cm working heights. From the postural risk assessment, the authors found that the tasks of mortar scooping and picking up the brick posed a higher risk level during working at foot height, as evidenced by evaluated RULA scores with higher joint angles in the upper arm and trunk. Conversely, working at 77 cm height was able to eliminate critical postures, thereby reducing the postural risk level from high to a low score of 4 across all tasks. Furthermore, musculoskeletal modeling simulations revealed that the shoulder joint bears the primary biomechanical demand over the tasks, peaking approximately 233 N at 0 cm height. Working at 77 cm height, JRFs were substantially reduced at the shoulder joint, while elbow and neck JRFs generally decreased or remained stable. Two-way ANOVA confirmed that both working height and task type had highly significant main and interaction effects (p < 0.001) on the reaction forces of the shoulder, elbow, and neck joints. Lower joint reaction forces contribute to reducing postural risk by releasing pressure on the upper body joints. Therefore, a working height approximately midway between the worker’s knee and waist height is recommended to minimize postural risk and joint reaction forces during wall construction tasks. In this study, the average of this anthropometrically defined height was 77 cm, and the recommendation should be interpreted relative to the worker’s body dimensions rather than as a fixed universal value.
Author Contributions
Conceptualization, M.S.R. and J.S.; methodology, M.S.R; software, M.S.R; validation, M.S.R., T.C. and J.S.; formal analysis, M.S.R.; investigation, J.S.; resources, M.S.R and J.S.; data curation, M.S.R; writing original draft preparation, M.S.R.; writing review and editing, T.C. and J.S.; visualization, M.S.R.; supervision, J.S.; project administration, J.S.; funding acquisition, J.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Human Subject Research Ethics Approval Committee of Kanazawa University, Japan (Approval number: 2023-8).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The data analyzed in this study are available on request from the corresponding author.
Acknowledgments
The authors would like to thank all participants for their contributions in this study.
Conflicts of Interest
The authors declare no conflicts of interest.
Declaration: AI tools were used solely for grammar and spelling-checking.
References
- Keyserling, W.M.; Brouwer, M.; Silverstein, B.A. The Effectiveness of a Joint Labor-Management Program in Controlling Awkward Postures of the Trunk, Neck, and Shoulders: Results of a Field Study. Int. J. Ind. Ergon. 1993, 11, 51–65. [Google Scholar] [CrossRef]
- Johansen, K.W.; Schultz, C.; Teizer, J. Hazard Ontology and 4D Benchmark Model for Facilitation of Automated Construction Safety Requirement Analysis. Comput.-Aided Civ. Infrastruct. Eng. 2023, 38, 2128–2144. [Google Scholar] [CrossRef]
- McAtamney, L.; Nigel Corlett, E. RULA: A Survey Method for the Investigation of Work-Related Upper Limb Disorders. Appl. Ergon. 1993, 24, 91–99. [Google Scholar] [CrossRef]
- Hignett, S.; McAtamney, L. Rapid Entire Body Assessment (REBA). Appl. Ergon. 2000, 31, 201–205. [Google Scholar] [CrossRef]
- Karhu, O.; Kansi, P.; Kuorinka, I. Correcting Working Postures in Industry: A Practical Method for Analysis. Appl. Ergon. 1977, 8, 199–201. [Google Scholar] [CrossRef]
- Sanchez-Lite, A.; Garcia, M.; Domingo, R.; Angel Sebastian, M. Novel Ergonomic Postural Assessment Method (NERPA) Using Product-Process Computer Aided Engineering for Ergonomic Workplace Design. PLoS ONE 2013, 8, e72703. [Google Scholar] [CrossRef]
- Adi, H.P.; Boogaard, F.C.; Schaap, E.; Hatmoko, J.U.D. Evaluation of Working Posture of Construction Workers: A Case Study on Wall Construction Using Lightweight Bricks. Civ. Eng. Archit. 2023, 11, 64–71. [Google Scholar] [CrossRef]
- Basahel, A.M. Investigation of Work-Related Musculoskeletal Disorders (MSDs) in Warehouse Workers in Saudi Arabia. Procedia Manuf. 2015, 3, 4643–4649. [Google Scholar] [CrossRef]
- Bao, S.; Howard, N.; Spielholz, P.; Silverstein, B. Two Posture Analysis Approaches and Their Application in a Modified Rapid Upper Limb Assessment Evaluation. Ergonomics 2007, 50, 2118–2136. [Google Scholar] [CrossRef]
- Intranuovo, G.; De Maria, L.; Facchini, F.; Giustiniano, A.; Caputi, A.; Birtolo, F.; Vimercati, L. Risk Assessment of Upper Limbs Repetitive Movements in a Fish Industry. BMC Res. Notes 2019, 12. [Google Scholar] [CrossRef]
- Li, J.; Bian, S.; Zeng, A.; Wang, C.; Pang, B.; Liu, W.; Lu, C. Human Pose Regression with Residual Log-Likelihood Estimation. In Proceedings of the 2021 IEEE/CVF International Conference on Computer Vision (ICCV); IEEE: Montreal, QC, Canada, October 2021. [Google Scholar]
- Rodrigues, P.B.; Xiao, Y.; Fukumura, Y.E.; Awada, M.; Aryal, A.; Becerik-Gerber, B.; Lucas, G.; Roll, S.C. Ergonomic Assessment of Office Worker Postures Using 3D Automated Joint Angle Assessment. Adv. Eng. Inform. 2022, 52, 101596. [Google Scholar] [CrossRef]
- Wang, Z.; Wang, W.; Chen, J.; Zhang, X.; Miao, Z. Posture Risk Assessment and Workload Estimation for Material Handling by Computer Vision. Int. J. Intell. Syst. 2023. [Google Scholar] [CrossRef]
- Neumann, W.P.; Wells, R.P.; Norman, R.W.; Frank, J.; Shannon, H.; Kerr, M.S. A Posture and Load Sampling Approach to Determining Low-Back Pain Risk in Occupational Settings. Int. J. Ind. Ergon. 2001, 27, 65–77. [Google Scholar] [CrossRef]
- Siddiqui, L.A.; Banerjee, A.; Chokhandre, P.; Unisa, S. Prevalence and Predictors of Musculoskeletal Disorders (MSDs) among Weavers of Varanasi, India: A Cross-Sectional Study. Clin. Epidemiol. Glob. Health 2021, 12, 100918. [Google Scholar] [CrossRef]
- Daruis, D.I. Prevalence of Work Related Musculoskeletal Disorders Symptoms among Construction Workers: A Case Study in Malaysia. 2014, 43. [Google Scholar]
- Alghadir, A.; Anwer, S. Prevalence of Musculoskeletal Pain in Construction Workers in Saudi Arabia. Sci. World J. 2015, 2015. [Google Scholar] [CrossRef]
- Andrasfay, T.; Raymo, N.; Goldman, N.; Pebley, A.R. Physical Work Conditions and Disparities in Later Life Functioning: Potential Pathways. SSM-Popul. Health 2021, 16, 100990. [Google Scholar] [CrossRef]
- Thamrin, Y.; Wahyu, A.; Russeng, S.S.; Wahyuni, A.; Hardianti, A. Ergonomics and Musculoskeletal Disorders among Seaweed Workers in Takalar Regency: A Mixed Method Approach. Med. Clínica Práctica 2020, 3, 100110. [Google Scholar] [CrossRef]
- Kihlberg, S.; Kjellberg, A.; Lindbeck, L. Pneumatic Tool Torque Reaction: Reaction Forces, Displacement, Muscle Activity and Discomfort in the Hand-Arm System. Appl. Ergon. 1993, 24, 165–173. [Google Scholar] [CrossRef]
- Chang, T.-W.; Chen, J.J.-G. Biomechanical Analysis of Dynamic Manual Materials Handling Model. J. Chin. Inst. Ind. Eng. 2004, 21, 475–483. [Google Scholar] [CrossRef]
- Ngo, B.P.T.; Yazdani, A.; Carlan, N.; Wells, R. Lifting Height as the Dominant Risk Factor for Low-Back Pain and Loading During Manual Materials Handling: A Scoping Review. IISE Trans. Occup. Ergon. Hum. Factors 2017, 5, 158–171. [Google Scholar] [CrossRef]
- Rahman, Md.S.; Yazaki, T.; Chihara, T.; Sakamoto, J. Evaluating Lumbar Biomechanics for Work-Related Musculoskeletal Disorders at Varying Working Heights During Wall Construction Tasks. Biomechanics 2025, 5, 58. [Google Scholar] [CrossRef]
- Perception Neuron 3 Hardware List. Available online: https://support.neuronmocap.com/hc/en-us/articles/4401815074203-Perception-Neuron-3-Hardware-List (accessed on 28 March 2025).
- Choo, C.Z.Y.; Chow, J.Y.; Komar, J. Validation of the Perception Neuron System for Full-Body Motion Capture. PLoS ONE 2022, 17, e0262730. [Google Scholar] [CrossRef]
- Wu, Y.; Tao, K.; Chen, Q.; Tian, Y.; Sun, L. A Comprehensive Analysis of the Validity and Reliability of the Perception Neuron Studio for Upper-Body Motion Capture. Sensors 2022, 22, 6954. [Google Scholar] [CrossRef]
- Damsgaard, M.; Rasmussen, J.; Christensen, S.T.; Surma, E.; De Zee, M. Analysis of Musculoskeletal Systems in the AnyBody Modeling System. Simul. Model. Pract. Theory 2006, 14, 1100–1111. [Google Scholar] [CrossRef]
- 19-3.Png|IIETA. Available online: https://www.iieta.org/file/108127 (accessed on 7 September 2026).
- AnyBody Technology. Features of Muscle Recruitment Algorithms. 2009. Available online: https://www.anybodytech.com/download/features-of-muscle-recruitment-algorithms/.
- Bassani, T.; Stucovitz, E.; Qian, Z.; Briguglio, M.; Galbusera, F. Validation of the AnyBody Full Body Musculoskeletal Model in Computing Lumbar Spine Loads at L4L5 Level. J. Biomech. 2017, 58, 89–96. [Google Scholar] [CrossRef]
- Damsgaard, M.; Rasmussen, J.; Christensen, S.T.; Surma, E.; De Zee, M. Analysis of Musculoskeletal Systems in the AnyBody Modeling System. Simul. Model. Pract. Theory 2006, 14, 1100–1111. [Google Scholar] [CrossRef]
- Mallapiang, F.; Azriful; Nildawati; Syarfaini; Muis, M.; Adriansyah. The Relationship of Posture Working with Musculoskeletal Disorders (MSDs) in the Weaver West Sulawesi Indonesia. Gac. Sanit. 2021, 35, S15–S18. [Google Scholar] [CrossRef]
- Kulkarni, V.S.; Devalkar, R.V. Postural Analysis of Building Construction Workers Using Ergonomics. Int. J. Constr. Manag. 2019, 19, 464–471. [Google Scholar] [CrossRef]
- Rahman, Md.S.; Uddin, Md.K.; Iqbal, M. Assessing Postural Risks in the Building Construction Sector: A Case Study in Bangladesh. Int. J. Occup. Saf. Health 2024, 14, 620–632. [Google Scholar] [CrossRef]
- Maciukiewicz, J.M.; Cudlip, A.C.; Chopp-Hurley, J.N.; Dickerson, C.R. Effects of Overhead Work Configuration on Muscle Activity during a Simulated Drilling Task. Appl. Ergon. 2016, 53, 10–16. [Google Scholar] [CrossRef]
- Skovlund, S.V.; Bláfoss, R.; Skals, S.; Jakobsen, M.D.; Andersen, L.L. The Importance of Lifting Height and Load Mass for Muscular Workload during Supermarket Stocking: Cross-Sectional Field Study. Int. J. Environ. Res. Public. Health 2022, 19, 3030. [Google Scholar] [CrossRef]
- Borrelli, S.; Putame, G.; Pascoletti, G.; Terzini, M.; Zanetti, E.M. In Silico Meta-Analysis of Boundary Conditions for Experimental Tests on the Lumbar Spine. Ann. Biomed. Eng. 2022, 50, 1243–1254. [Google Scholar] [CrossRef]
- Brambilla, C.; Lavit Nicora, M.; Storm, F.; Reni, G.; Malosio, M.; Scano, A. Biomechanical Assessments of the Upper Limb for Determining Fatigue, Strain and Effort from the Laboratory to the Industrial Working Place: A Systematic Review. Bioengineering 2023, 10, 445. [Google Scholar] [CrossRef]
- Arvidsson, I.; Dahlqvist, C.; Enquist, H.; Nordander, C. Action Levels for the Prevention of Work-Related Musculoskeletal Disorders in the Neck and Upper Extremities: A Proposal. Ann. Work Expo. Health 2021, 65, 741–747. [Google Scholar] [CrossRef]
- van der Molen, H.F.; Grouwstra, R.; Kuijer, P.P.F.M.; Sluiter, J.K.; Frings-Dresen, M.H.W. Efficacy of Adjusting Working Height and Mechanizing of Transport on Physical Work Demands and Local Discomfort in Construction Work. Ergonomics 2004, 47, 772–783. [Google Scholar] [CrossRef]
- Sporrong, H.; Sandsjö, L.; Kadefors, R.; Herberts, P. Assessment of Workload and Arm Position during Different Work Sequences: A Study with Portable Devices on Construction Workers. Appl. Ergon. 1999, 30, 495–503. [Google Scholar] [CrossRef]
- Brandt, M.; Bláfoss, R.; Jakobsen, M.D.; Samani, A.; Ajslev, J.Z.N.; Madeleine, P.; Andersen, L.L. Influence of Brick Laying Height on Biomechanical Load in Masons: Cross-Sectional Field Study with Technical Measurements. Work 2024, 79, 459–470. [Google Scholar] [CrossRef]
Figure 1.
Experimental setup in the laboratory environment: (left) foot level (0 cm) working height, (right) 77 cm working height for mortar and bricks.
Figure 1.
Experimental setup in the laboratory environment: (left) foot level (0 cm) working height, (right) 77 cm working height for mortar and bricks.
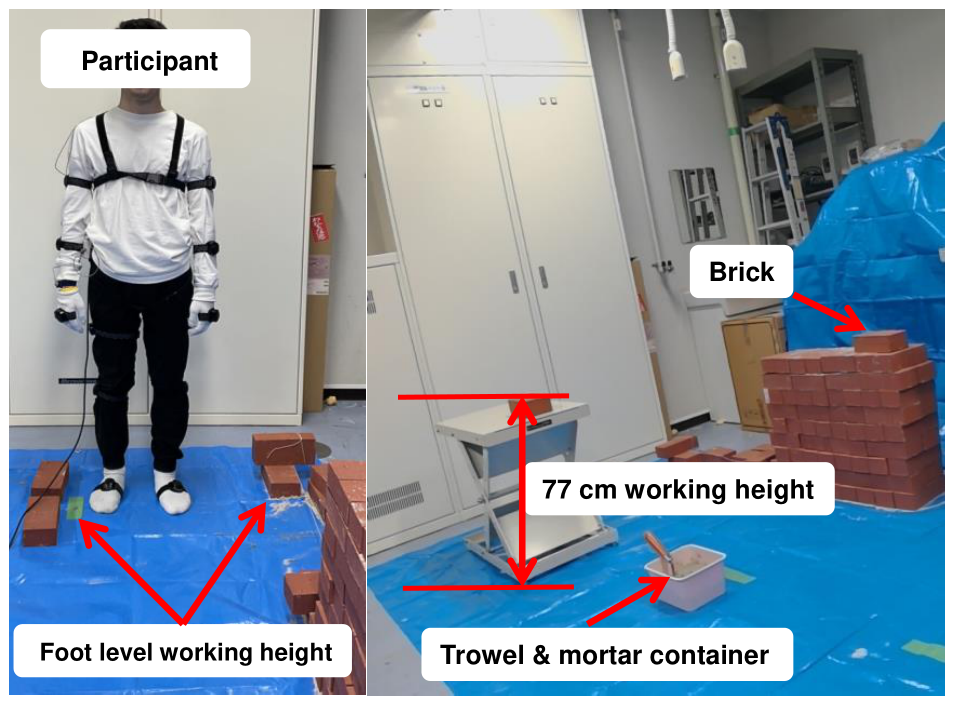
Figure 2.
RULA Scoring chart.
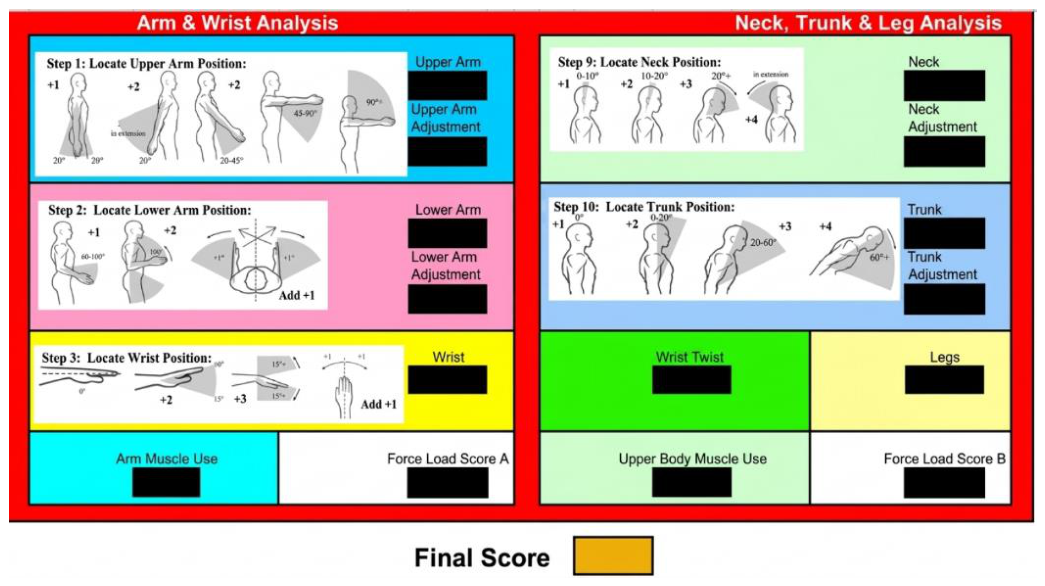
Figure 3.
Actual body movements and 3D estimated postures of the selected tasks while working at 0 cm (foot) height.
Figure 3.
Actual body movements and 3D estimated postures of the selected tasks while working at 0 cm (foot) height.
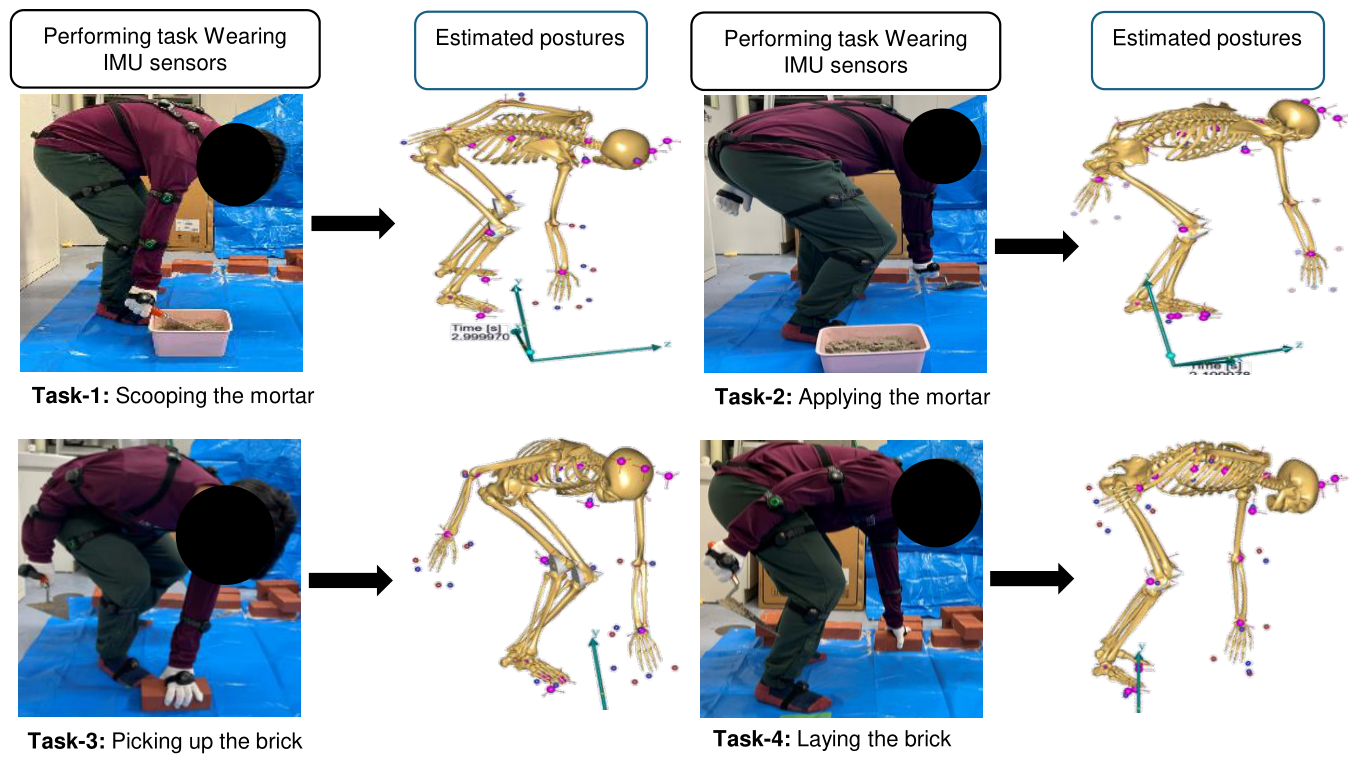
Figure 4.
Actual body movements and 3D estimated postures of the selected tasks during work at 77 cm height.
Figure 4.
Actual body movements and 3D estimated postures of the selected tasks during work at 77 cm height.
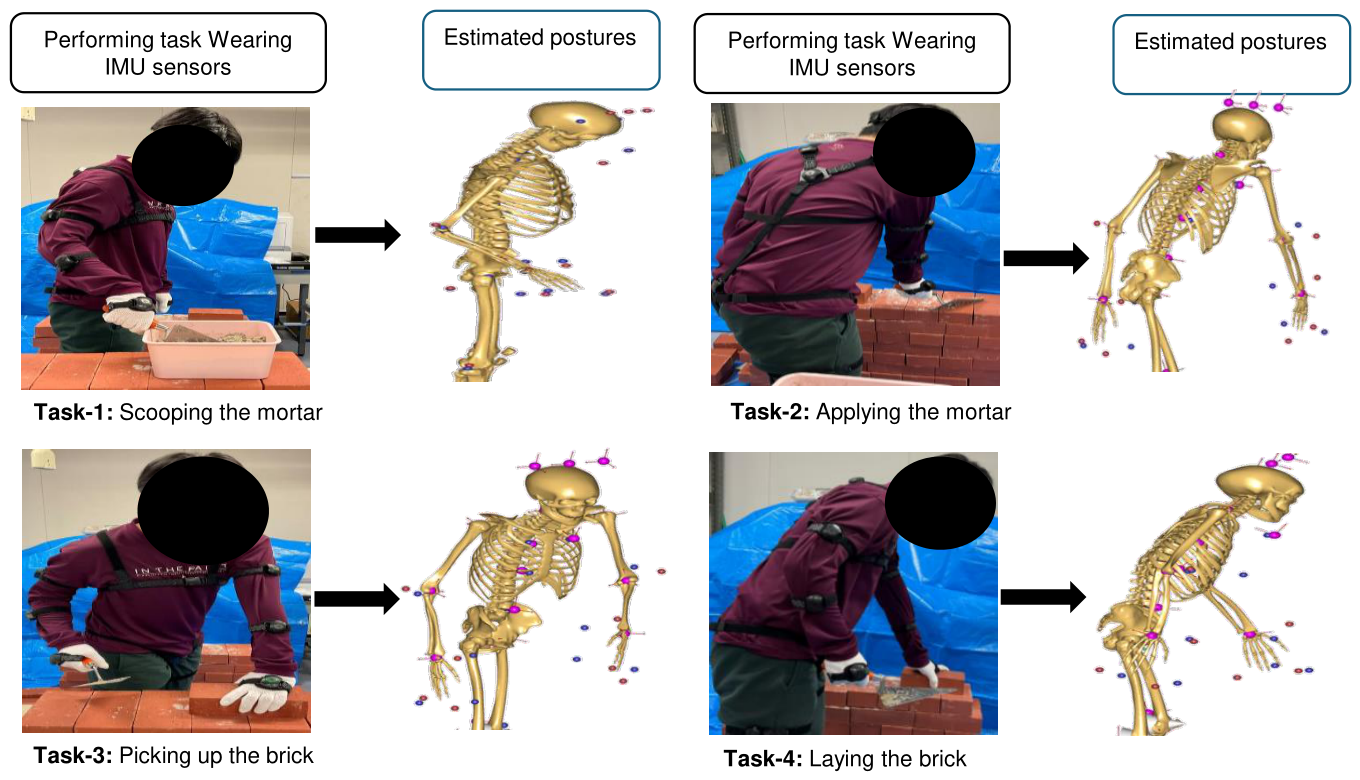
Figure 5.
Joint reaction forces (%BW) at the shoulder, elbow, and neck under different working heights (0 and 77 cm) across four construction tasks. Error bars indicate standard deviations.
Figure 5.
Joint reaction forces (%BW) at the shoulder, elbow, and neck under different working heights (0 and 77 cm) across four construction tasks. Error bars indicate standard deviations.
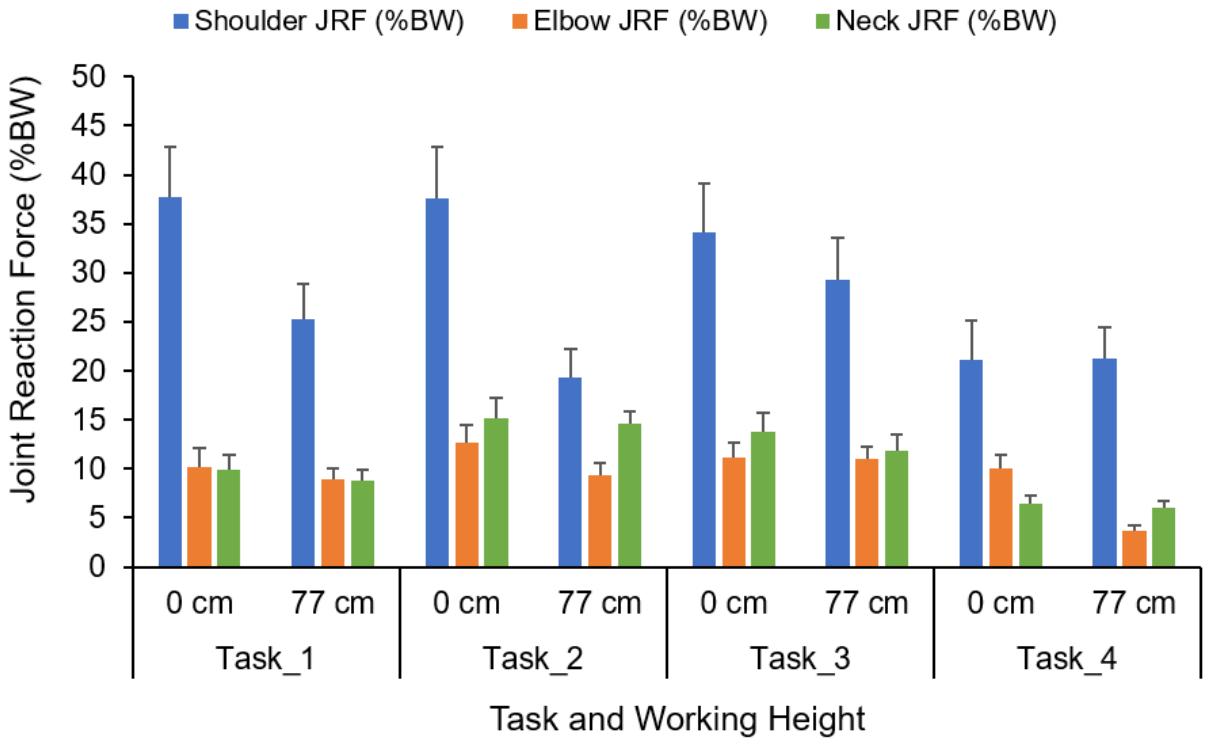

Table 1.
Participant details.
| Participant No |
Age (years) |
Height (cm) |
Weight (kg) | Foot Level Height (cm) | Knee Level Height (cm) | Waist Level Height (cm) | Shoulder Level Height (cm) |
| 01 | 21 | 170 | 59.6 | 0 0 0 0 0 0 0 0 0 0 0 0 0 0 0 0 0 0 |
45 | 105 | 142 |
| 02 | 20 | 174.4 | 63.1 | 50 | 105 | 153 | |
| 03 | 23 | 168.5 | 52.2 | 47 | 100 | 143 | |
| 04 | 21 | 170 | 77.1 | 52 | 110 | 141 | |
| 05 | 23 | 166.3 | 51.8 | 48 | 113 | 145 | |
| 06 | 23 | 182.4 | 65.5 | 48 | 118 | 145 | |
| 07 | 23 | 164.3 | 52.8 | 45 | 108 | 140 | |
| 08 | 24 | 172.1 | 82.0 | 45 | 100 | 136 | |
| 09 | 21 | 182.3 | 74.6 | 47 | 99 | 136 | |
| 10 | 21 | 167 | 64 | 45 | 100 | 145 | |
| 11 | 21 | 177 | 68.8 | 47 | 115 | 140 | |
| 12 | 21 | 170 | 62.2 | 50 | 99 | 138 | |
| Average | 21.83 | 172.03 | 64.48 | 0 | 47 | 107 | 142 |
Table 2.
The RULA score, risk level, and associated required actions.
| RULA Score | Risk Level | Action |
| 1-2 | Negligible risk | No action required |
| 3-4 | Low risk | Change may be needed |
| 5-6 | Medium risk | Further investigation, change soon |
| 7≤ | Very high risk | Implement change now |
Table 3.
Joint angles (mean ± SD), RULA scores (mode/median), and risk level distribution across all tasks 1-4 at 0 cm working height.
Table 3.
Joint angles (mean ± SD), RULA scores (mode/median), and risk level distribution across all tasks 1-4 at 0 cm working height.
| Tasks | Upper Arm (°) | Lower Arm (°) | Wrist (°) | Neck (°) | Trunk (°) | RULA Score (Mode) | RULA Score (Median) | Risk Distribution (% of subjects) |
| Task-1: Scooping mortar | 54.22±5.99 | 19.69±3.1 | 3.23±0.9 | 15.59±2.4 | 40.69±4.7 | 7 | 7 | 100% High Risk (Score 7) |
| Task-2: Applying mortar | 64.94± 5.4 | 29.21±4.0 | 2.39±0.51 | 2.60±1.2 | 42.58±5.1 | 6 | 6 | 83.3% Medium (Score 6), 16.7% High (Score 7) |
| Task-3: Picking up brick | 78.97±7.1 | 2.57±0.91 | 2.11±0.39 | 15.30±2.7 | 45.28±4.8 | 7 | 7 | 100% High Risk (Score 7) |
| Task-4: Laying brick | 45.99±4.7 | 2.46±0.71 | 2.28±0.59 | 10.31±1.8 | 39.31±3.7 | 6 | 6 | 91.7% Medium (Score 6), 8.3% Low (Score 4) |
Table 4.
Joint angles (mean ± SD), RULA scores (mode/median), and risk level distribution across all tasks 1-4 at 77 cm working height.
Table 4.
Joint angles (mean ± SD), RULA scores (mode/median), and risk level distribution across all tasks 1-4 at 77 cm working height.
| Tasks | Upper Arm (°) | Lower Arm (°) | Wrist (°) | Neck (°) | Trunk (°) | RULA Score (Mode) | RULA Score (Median) | Risk Distribution (% of Subjects) |
| Task-1: Scooping mortar | 19.95±3.2 | 84.38±6.4 | 3.21±0.6 | 10.51±1.7 | 6.95±1.1 | 4 | 4 | 100% Low Risk (Score 3–4) |
| Task-2: Applying mortar | 60.16±5.7 | 30.68±3.8 | 3.45±0.5 | 2.56±0.8 | 7.13±1.4 | 4 | 4 | 91.7% Low (Score 4), 8.3% Medium (Score 5) |
| Task-3: Picking up brick | 65.30±6.0 | 26.96±3.3 | 4.36±0.7 | 6.96±1.1 | 7.21±1.4 | 4 | 4 | 100% Low Risk (Score 3–4) |
| Task-4: Laying brick | 29.19±3.4 | 23.10±2.7 | 2.68±0.4 | 4.89±0.99 | 6.12±1.2 | 4 | 4 | 100% Low Risk (Score 3–4) |
Table 5.
Absolute joint reaction forces across all tasks and two working heights.
| Task | Working Height (cm) |
Joint Reaction Force (JRF) (Mean ± SD) | ||
| Shoulder (N) | Elbow (N) | Neck (N) | ||
| Task_1 | 0 | 233.82 ± 9.41 | 62.75 ± 3.16 | 61.75 ± 1.72 |
| 77 | 175.70 ± 2.14 | 55.50 ± 2.68 | 54.60 ± 1.90 | |
| Task_2 | 0 | 233.00 ± 4.26 | 79.17 ± 3.65 | 93.33 ± 4.32 |
| 77 | 119.87 ± 0.76 | 57.75 ± 2.15 | 91.00 ± 1.94 | |
| Task_3 | 0 | 211.80 ± 1.88 | 69.00 ± 2.77 | 85.25 ± 1.46 |
| 77 | 181.57 ± 1.58 | 68.17 ± 2.88 | 73.70 ± 1.74 | |
| Task_4 | 0 | 168.00 ± 1.85 | 62.14 ± 1.12 | 40.17 ± 2.98 |
| 77 | 132.05 ± 1.10 | 23.18 ± 1.48 | 37.32 ± 1.55 | |
SD = Standard Deviation, N = Newton.
Table 6.
Summary of Two-way ANOVA results for joint reaction force.
| Dependent Variables | Factor | F | P-value | Partialη2 |
| Shoulder JRF | Working Height | 6442.38 | <0.001** | 0.98 |
| Tasks | 742.85 | <0.001** | 0.96 | |
| Working Height × Tasks | 589.65 | <0.001** | 0.95 | |
| Elbow JRF | Working Height | 1029.15 | <0.001** | 0.92 |
| Tasks | 522.62 | <0.001** | 0.95 | |
| Working Height × Tasks | 251.23 | <0.001** | 0.90 | |
| Neck JRF | Working Height | 150.51 | <0.001** | 0.63 |
| Tasks | 2343.60 | <0.001** | 0.99 | |
| Working Height × Tasks | 19.52 | <0.001** | 0.40 |
Note: **Significant at p<0.001. JRF = Joint Reaction Force; Partial η2 = Partial eta squared.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.