
Submitted:
10 August 2026
Posted:
11 August 2026
You are already at the latest version
Abstract
Introduction: Scimitar syndrome is a rare congenital form of partial anomalous pulmonary venous return characterized by right pulmonary venous drainage into the inferior vena cava. This abnormal shunting leads to right sided volume overload and increased risk of supraventricular arrhythmias, particularly in adolescents and adults. However, existing studies do not clearly describe reported arrhythmia patterns or how heart rhythm changes over time. Objectives: This systematic review aims to describe how congenital cardiopulmonary abnormalities in patients with Scimitar syndrome contribute to atrial remodeling and the development of atrial and supraventricular arrhythmias. Methods A literature review search was conducted in PubMed. Relevant data were extracted after screening titles, 308 abstracts were assessed using inclusion and exclusion criteria. Full text screening was performed for 94 articles, Inclusion criteria consisted of patients with Scimitar syndrome. Exclusion criteria included literature review, animal studies and non-English articles. Results: Studies consistently showed that Scimitar syndrome is associated with right atrial enlargement and atrial remodeling due to chronic right-sided volume overload. These changes were linked to an increased burden of atrial and supraventricular arrhythmias, most commonly atrial fibrillation and atrial flutter. Arrhythmia risk was greater in patients with associated abnormalities such as atrial septal defects or pulmonary hypertension. Discussion and Conclusion: Scimitar syndrome often presents with atrial remodeling and cardiac abnormalities that increase the risk of arrhythmias, especially atrial fibrillation and atrial flutter. Given that scimitar syndrome can remain undiagnosed until adulthood, future studies should focus on the specific predictors for arrhythmia development to improve long-term electrophysiological outcomes.
Keywords:
arrhythmia
; scimitar syndrome
; congenital heart diseases
; arrhythmia burden
; atrial remodeling
; intervention
; electrophysiology
; EP
; cardiology
; pediatric cardiology
I. Introduction and Objectives
Scimitar syndrome is a rare congenital cardiopulmonary anomaly characterized by partial anomalous pulmonary venous return (PAPVR) in which one or more right pulmonary veins drain anomalously into the inferior vena cava [1,2,3]. This aberrant venous connection results in a left-to-right shunt that produces chronic right-sided volume overload, progressive enlargement of right-sided cardiac chambers, and a spectrum of cardiopulmonary manifestations that may range from asymptomatic childhood presentation to significant adult morbidity [2,3]. The syndrome is frequently accompanied by additional structural abnormalities including atrial septal defects, right lung hypoplasia, and pulmonary hypertension, all of which further contribute to hemodynamic burden [4,5].
Chronic atrial stretch and remodeling are well-established substrates for the development of supraventricular arrhythmias [5,6,7]. Progressive right atrial dilation promotes fibrosis, conduction of heterogeneity, and electrical instability, creating conditions favorable for atrial fibrillation, atrial flutter, and other supraventricular tachyarrhythmias [6,7,8]. These mechanisms have been extensively described in broader congenital heart disease populations; however, their specific manifestation in Scimitar syndrome remains incompletely characterized [8,9,10]. As survival into adulthood has become increasingly common among patients with congenital heart disease, arrhythmia burden has emerged as a major determinant of long-term outcomes, quality of life, and need for intervention [9,10,11].
Despite the recognized association between structural congenital heart disease and arrhythmogenesis, the literature describing arrhythmias in Scimitar syndrome is fragmented and largely limited to isolated case reports and small retrospective series [11,12,13]. Reported rhythm disturbances range from paroxysmal atrial tachycardia to sustained atrial fibrillation and flutter, yet there is no unified description of prevalence, clinical predictors, or natural history [12,13,14]. Furthermore, the impact of corrective surgical or catheter-based interventions on long-term electrophysiologic outcomes remains uncertain [13,14,15]. Consequently, clinicians lack evidence-based guidance regarding optimal rhythm surveillance, timing of intervention, and risk stratification in this unique patient population [14,15,16].
A comprehensive synthesis of available data is therefore needed to better define the relationship between the anatomic features of Scimitar syndrome and the development of atrial arrhythmias. Systematic evaluation of published reports can help clarify which structural and clinical characteristics confer the greatest arrhythmic risk, how arrhythmia patterns evolve over time, and whether specific management strategies influence outcomes [15,16,17]. Establishing such a framework is particularly important as the population of adults with congenital heart disease continues to expand, and arrhythmias increasingly become a primary driver of morbidity [16,17,18,19].
The present literature review aims to consolidate and critically evaluate published evidence regarding atrial remodeling and supraventricular arrhythmias in patients with Scimitar syndrome. By characterizing reported arrhythmia types, associated structural abnormalities, and clinical outcomes, this review seeks to provide a clearer understanding of the electrophysiologic implications of Scimitar syndrome and to identify key gaps that should guide future research and clinical practice [17,18,19,20].
II. Methods
This study was conducted as a literature review, aiming to synthesize clinical evidence on atrial remodeling and arrhythmia burden in patients with Scimitar syndrome. A predefined protocol guided the search, selection, and extraction processes to ensure transparency, reproducibility, and methodological rigor. Electronic searches were conducted in PubMed to identify peer-reviewed clinical studies. The search strategy included terms related to both the underlying congenital anomaly and arrhythmic manifestations, such as “Scimitar syndrome,” “partial anomalous pulmonary venous return,” “atrial remodeling,” “atrial arrhythmia,” “supraventricular arrhythmia,” and related synonyms. Boolean operators (AND/OR) were applied to refine searches and ensure identification of studies addressing both structural atrial changes and arrhythmia outcomes. Searches were iteratively refined to maximize relevance while minimizing retrieval of irrelevant studies.
Studies were included if they reported on human patients of any age with a confirmed diagnosis of Scimitar syndrome and clinical arrhythmia outcomes. Eligible study designs included randomized controlled trials, observational cohorts, case series, and case reports providing original clinical data, including patient demographics, associated cardiac anomalies, arrhythmia types, interventions performed, and rhythm outcomes. Exclusion criteria were narrative reviews, animal studies, abstracts without full-text availability, and non-English publications. Given the rarity of Scimitar syndrome and the limited number of studies reporting arrhythmic outcomes, relevant physiological concepts from related conditions, including left heart volume overload and atrial septal defects were also considered to contextualize findings. These concepts informed the interpretation of structural and electrophysiologic patterns but did not influence eligibility criteria or the systematic search process. Inclusion and exclusion criteria are summarized in Table 1.
The screening and selection process adhered to a two-stage review. Titles and abstracts of all retrieved articles were screened independently by five reviewers against predefined inclusion and exclusion criteria, and discrepancies were resolved by consensus. Of the 308 abstracts initially identified, 94 met the eligibility criteria and were selected for full-text review. Reference lists of included studies were also manually screened to capture additional relevant publications. The overall selection process is depicted in the flow diagram Figure 1.
Data extraction was conducted using a standardized form to ensure consistency and completeness. Identified limitations were documented and considered in interpretation rather than used as exclusion criteria, maintaining inclusivity while signaling methodological rigor. This approach provides a transparent and reproducible methodology while maintaining flexibility for the heterogeneity inherent to rare congenital cardiac conditions, enabling a comprehensive synthesis of structural and arrhythmic outcomes in Scimitar syndrome.
III. Results
1. Anatomy and Pathophysiologic Mechanisms
Scimitar syndrome represents a complex variant of partial anomalous pulmonary venous return (PAPVR), characterized by drainage of right pulmonary veins into the inferior vena cava, resulting in a left-to-right shunt [32,33,34,35,36]. However, across the included studies, this anomaly is consistently described not as an isolated defect, but as part of a broader developmental disorder involving the lung, pulmonary vasculature, and systemic arterial supply [41,42,43,44].
The pathophysiology is therefore inherently multifactorial. In addition to anomalous venous return, several mechanisms simultaneously contribute to disease burden, including systemic arterial collaterals, hypoplasia of the right lung and pulmonary artery, and, in some cases, pulmonary venous obstruction [23,25,41,42,43,44]. These interacting abnormalities reduce the effective pulmonary vascular bed while increasing pulmonary blood flow, producing a variable and often unpredictable hemodynamic profile rather than a uniform disease process [37,40,43].
Importantly, multiple studies emphasize that this heterogeneity explains the wide spectrum of clinical severity, as no single mechanism alone determines outcomes; instead, disease expression reflects the cumulative effect of structural and vascular abnormalities [42].
2. Clinical Spectrum and Disease Expression
The clinical presentation of scimitar syndrome spans a continuous spectrum from severe infantile disease to incidental adult diagnosis, rather than representing two distinct entities [21,33,35,40].
In infants, studies consistently report early presentation with respiratory distress, pulmonary hypertension, and failure to thrive, driven by large shunts and associated structural abnormalities [35,40,43]. These cases often require early intervention due to significant hemodynamic compromise.
In contrast, adult presentations are frequently delayed and may remain clinically silent for decades. Several studies describe patients diagnosed incidentally or after evaluation for unrelated symptoms, such as dyspnea or arrhythmia [21,23,34]. The severity of symptoms in adulthood correlates more strongly with shunt magnitude and associated anomalies than with age itself, supporting the concept that disease progression is gradual and dependent on cumulative hemodynamic burden [22,33,40].
3. Hemodynamic Burden, Right Heart Remodeling, and Pulmonary Hypertension
Across studies, a central finding is that chronic left-to-right shunting leads to progressive right-sided volume overload, resulting in right atrial and ventricular dilation and, in some cases, pulmonary hypertension (PH) [23,24,25,26,41].
However, the development of PH is not universal. Evidence suggests that pulmonary vascular disease depends on total shunt burden, extent of anomalous venous drainage, and the presence of additional risk factors such as lung hypoplasia or systemic collaterals [24,25,37]. In more severe cases, sustained increases in pulmonary blood flow and vascular remodeling lead to elevated pulmonary vascular resistance and irreversible PH, which is consistently identified as a major determinant of morbidity and mortality [36,41,43].
Mechanistically, PH in scimitar syndrome arises from overlapping contributors, including increased pulmonary flow, reduced vascular capacity, and venous obstruction [36,41,44]. This multifactorial origin distinguishes it from other forms of pulmonary hypertension and complicates both diagnosis and management.
4. Diagnostic Challenges and the Role of Multimodal Imaging
A consistent theme across the literature is the under-recognition of anomalous pulmonary venous return, particularly in adults [21,27,28,29]. Several studies demonstrate that PAPVR may remain undetected even when present on imaging, especially if pulmonary venous pathways are not systematically evaluated [27,28].
Echocardiography is typically the first-line modality, but its limitations in visualizing extracardiac structures frequently necessitate further imaging [23,40]. Advanced modalities such as CT and cardiac MRI are repeatedly shown to provide definitive anatomical characterization, accurate shunt quantification, and assessment of right heart remodeling [28,29,34].
Cardiac catheterization remains the gold standard for hemodynamic evaluation, particularly in complex or symptomatic cases, as it allows direct measurement of pulmonary pressures and vascular resistance [34,36]. Collectively, the evidence supports a multimodal imaging approach, especially when initial studies are inconclusive or when right heart enlargement is unexplained [27,28,29].
5. Structural Remodeling and Arrhythmogenesis
Chronic right-sided volume overload creates a structural substrate for atrial remodeling and arrhythmia development [22,25,30]. Multiple studies suggest that prolonged atrial dilation and fibrosis contribute to electrical instability, predisposing patients to atrial fibrillation and other supraventricular arrhythmias [22,30].
Importantly, arrhythmias are often the first clinical manifestation in adults, prompting further investigation that ultimately reveals underlying congenital anatomy [22,23]. This pattern highlights the role of scimitar syndrome as a latent structural condition that may only become clinically apparent through secondary complications.
In addition to structural remodeling, emerging evidence suggests that anomalous pulmonary venous connections themselves may contribute to arrhythmogenesis, further complicating management strategies [30].
6. Management Strategies and Individualized Treatment
Management approaches vary significantly depending on symptom severity and hemodynamic impact, reflecting the heterogeneity of the condition [35,40,41].
Asymptomatic patients with small shunts are often managed conservatively with surveillance, while intervention is recommended in patients with significant shunting, pulmonary hypertension, or right heart dysfunction [35,40]. Treatment strategies include embolization of systemic collaterals and surgical redirection of pulmonary venous flow to the left atrium [40,41].
The decision to intervene is primarily guided by shunt magnitude and hemodynamic burden, often quantified using Qp:Qs ratios and invasive measurements [34,36]. This reinforces the importance of comprehensive evaluation prior to treatment selection.
7. Surgical Outcomes, Technique Considerations, and Complications
Surgical repair is generally associated with excellent survival and low perioperative mortality; however, long-term outcomes are influenced by both anatomy and operative technique [25,30].
Across studies, common postoperative complications include pulmonary vein stenosis, residual shunting, and arrhythmias [25,36]. Pulmonary vein obstruction is consistently identified as one of the most significant complications, often necessitating reintervention and negatively impacting prognosis [25,30,36].
Importantly, multiple studies suggest that surgical techniques play a critical role in outcomes. Approaches that preserve venous flow and minimize injury to conduction pathways are associated with improved rhythm outcomes and reduced risk of obstruction [30]. These findings support an individualized, anatomy-based surgical approach rather than a single standardized technique.
8. Long-Term Outcomes and Prognosis
Prognosis varies widely and is strongly influenced by age at presentation, shunt magnitude, and the presence of pulmonary hypertension [35,36,43].
Infantile cases are associated with higher morbidity and mortality due to severe hemodynamic burden, while many adults experience a relatively benign course, particularly in the absence of significant shunting or associated anomalies [21,35]. However, the development of pulmonary hypertension or complex structural abnormalities significantly worsens long-term outcomes [36,43].
Even after successful intervention, studies emphasize the need for long-term surveillance, as late complications such as pulmonary vein stenosis, recurrent shunting, and arrhythmias may develop years after treatment [36,43]. This underscores that scimitar syndrome is not a static condition, but one requiring ongoing multidisciplinary management.
IV. Discussion
Scimitar syndrome shows a consistent association with atrial and other supraventricular arrhythmias, and the pattern across studies supports right atrial remodeling as a central mechanism [32,35]. Across cohorts, chronic right sided volume overload from left to right shunting is repeatedly linked with right atrial and right ventricular dilation, elevated Qp/Qs ratios, and increased pulmonary artery pressures, indicating a sustained hemodynamic substrate that plausibly drives progressive atrial change over time [33,34].
Taken together, the findings support a mechanistic framework in which persistent volume loading leads to atrial dilation, structural remodeling including fibrosis, and subsequent electrical instability that manifests as atrial fibrillation, atrial flutter, and related supraventricular tachyarrhythmias [35,44]. This trajectory mirrors remodeling driven arrhythmogenesis described across other congenital heart disease populations, where rhythm disease increasingly contributes to long term morbidity as patients survive into adolescence and adulthood [32,33].
Clinically, the evidence supports early and continued rhythm surveillance as part of routine follow up, particularly for adolescents and adults, given that arrhythmias may be intermittent and asymptomatic and can emerge after years of abnormal loading [32,35]. This has direct relevance for adult congenital heart disease care, where longitudinal electrophysiologic monitoring and timely detection of atrial arrhythmias are central to reducing downstream complications and guiding management [33].
Arrhythmia risk appears nonuniform and is consistently higher when scimitar syndrome coexists with associated defects, especially atrial septal defect and pulmonary hypertension, which likely increase the magnitude and duration of right atrial stretch and pressure exposure [37]. Reports also describe higher risk in the presence of systemic arterial supply to the right lung or more severe right lung hypoplasia, further supporting the role of anatomic and hemodynamic modifiers in shaping arrhythmia burden [33].
Rhythm outcomes after intervention remain variable. Early postoperative atrial arrhythmias are described in surgical cohorts, while late onset arrhythmias are also reported years after repair or in medically managed patients with persistent shunting, suggesting that repair may reduce ongoing hemodynamic stress but does not reliably eliminate arrhythmia risk once atrial remodeling is established [35,42,44].
Interpretation is limited by the predominance of case reports and small retrospective series, with heterogeneous rhythm monitoring strategies, variable follow up, and nonstandard definitions of remodeling and arrhythmia outcomes, which restricts prevalence estimates and limits comparison across management strategies [32]. Future work should prioritize prospective registries and standardized rhythm monitoring protocols paired with uniform baseline and longitudinal atrial measurements, stratified by key anatomic and hemodynamic modifiers, to clarify predictors of arrhythmia progression and to define long term rhythm outcomes after repair versus conservative management [33,34].
V. Conclusions
In conclusion, this systematic review aimed to describe how congenital cardiopulmonary abnormalities in patients with Scimitar syndrome contribute to atrial remodeling and the development of atrial and supraventricular arrhythmias. Studies consistently showed that Scimitar syndrome is associated with right atrial enlargement and atrial remodeling due to chronic right-sided volume overload. These changes were linked to an increased burden of atrial and supraventricular arrhythmias, most commonly atrial fibrillation and atrial flutter. Arrhythmia risk was greater in patients with associated abnormalities such as atrial septal defects or pulmonary hypertension. From a clinical perspective, arrhythmias represent a major, under-characterized source of morbidity, and so standardized systematic rhythm surveillance should be integrated into long-term management of this Scimitar syndrome. Proactive monitoring strategies may facilitate earlier detection and intervention, with potential implications for symptom control and overall outcomes.
References
- Dupuis, C.; Charaf, L.A.; Brevière, G.M.; Abou, P. The “scimitar syndrome.” Three new cases and a review of the literature. Medicine 1992, 71(5), 315–327. [Google Scholar]
- Dillman, J.R.; Yarram, S.G.; Hernandez, R.J. Imaging of scimitar syndrome. Pediatr. Radiol. 2009, 39(6), 529–537. [Google Scholar]
- Najm, H.K.; Williams, W.G.; Coles, J.G.; Rebeyka, I.M.; Freedom, R.M. Scimitar syndrome: twenty years’ experience and results of repair. J. Thorac. Cardiovasc Surg. 1996, 112(5), 1161–1168. [Google Scholar] [CrossRef] [PubMed]
- Gatzoulis, M.A.; Webb, G.D.; Daubeney, P.E.F. Diagnosis and Management of Adult Congenital Heart Disease, 3rd ed.; Elsevier: Philadelphia, 2018. [Google Scholar]
- Khairy, P.; Van Hare, G.F.; Balaji, S.; et al. PACES/HRS expert consensus statement on the management of arrhythmias in adult congenital heart disease. Heart Rhythm. 2014, 11(10), e102–e165. [Google Scholar] [CrossRef] [PubMed]
- Triedman, J.K. Arrhythmias in adults with congenital heart disease. Heart 2002, 87(4), 383–389. [Google Scholar] [CrossRef] [PubMed]
- Bouchardy, J.; Therrien, J.; Pilote, L.; et al. Atrial arrhythmias in adults with congenital heart disease. Circulation 2009, 120(17), 1679–1686. [Google Scholar] [CrossRef] [PubMed]
- Warnes, C.A. The adult with congenital heart disease. J. Am. Coll. Cardiol. 2005, 46(1), 1–8. [Google Scholar] [CrossRef] [PubMed]
- Giamberti, A.; Chessa, M.; Abella, R.; et al. Scimitar syndrome: surgical repair and long-term results. Ann. Thorac. Surg. 2003, 75(2), 580–584. [Google Scholar]
- Vida, V.L.; Padalino, M.A.; Boccuzzo, G.; et al. Scimitar syndrome: a European multicenter study. Circulation 2010, 122(12), 1159–1166. [Google Scholar] [CrossRef]
- Al-Mohaissen, M.A.; Aboulhosn, J.A. Scimitar syndrome: a comprehensive review. Congenit Heart Dis. 2017, 12(4), 397–407. [Google Scholar] [CrossRef]
- Majdalany, D.S.; Phillips, S.D.; Dearani, J.A.; Connolly, H.M. Scimitar syndrome in adults. Congenit Heart Dis. 2010, 5(5), 490–495. [Google Scholar]
- El-Kersh, K.; Homsy, E.; Daniels, C.; Smith, J. Adult presentation of scimitar syndrome with atrial arrhythmia. Cardiol. Res. Pract. 2012, 2012, 1–4. [Google Scholar]
- Ho, M.L.; Bhalla, S.; Bierhals, A.; Gutierrez, F. MDCT of partial anomalous pulmonary venous return. AJR Am. J. Roentgenol. 2009, 192(5), 1272–1278. [Google Scholar]
- Warnes, C.A.; Williams, R.G.; Bashore, T.M.; et al. ACC/AHA guidelines for adults with congenital heart disease. J. Am. Coll. Cardiol. 2008, 52(23), e143–e263. [Google Scholar] [CrossRef] [PubMed]
- Marelli, A.J.; Ionescu-Ittu, R.; Mackie, A.S.; et al. Lifetime prevalence of congenital heart disease. Circulation 2014, 130(9), 749–756. [Google Scholar] [CrossRef] [PubMed]
- Khairy, P. Supraventricular tachyarrhythmias in adult congenital heart disease. Card. Electrophysiol. Clin. 2017, 9(2), 279–293. [Google Scholar] [CrossRef] [PubMed]
- Triedman, J.K.; Alexander, M.E.; Berul, C.I. Supraventricular tachycardia in congenital heart disease. J. Cardiovasc Electrophysiol. 2002, 13(9), 887–896. [Google Scholar]
- Brida, M.; Gatzoulis, M.A. Adult congenital heart disease: past, present, and future. Int. J. Cardiol. 2019, 283, 95–101. [Google Scholar]
- Zipes, D.P.; Jalife, J. Cardiac Electrophysiology: From Cell to Bedside, 7th ed.; Elsevier: Philadelphia, 2018. [Google Scholar]
- Pace Napoleone, C.; Mariucci, E.; Angeli, E.; Oppido, G.; D. Gargiulo, G. Sinus node dysfunction after partial anomalous pulmonary venous connection repair. Sci. J. Thorac. Cardiovasc. Surg. 2013. [Google Scholar] [CrossRef] [PubMed]
- Akam-Venkata, J.; Turner, D.R.; Joshi, A.; Aggarwal, S.; Gupta, P. Diagnosis and Management of the Unligated Vertical Vein in Repaired Total Anomalous Pulmonary Venous Connection. World J. Pediatr. Congenit. Heart Surg. 2019, 11(4), NP229–31. [Google Scholar] [CrossRef] [PubMed]
- Ho, M.L.; Bhalla, S.; Bierhals, A.; Gutierrez, F. MDCT of Partial Anomalous Pulmonary Venous Return (PAPVR) in Adults. J. Thorac. Imaging 2009, 24(2), 89–95. [Google Scholar] [CrossRef] [PubMed]
- Graham, G.; Dearani, J.A.; Mathew, J.; Miranda, W.R.; King, K.S.; Schaff, H.V.; et al. Partial Anomalous Pulmonary Venous Connection With Intact Atrial Septum: Early and Midterm Outcomes. Ann. Thorac. Surg. 2022, 115(6), 1479–84. [Google Scholar] [PubMed]
- Schwill, S.; Prete, J.D.; Cooley, D.A.; Morales, D.L. Two Scimitar Veins in an Adult: Repair through a Right Thoracotomy without Cardiopulmonary Bypass. Tex. Heart Inst. J. [Internet] 2026, 37(3), 358. [Google Scholar]
- Vida, V.L.; Guariento, A.; Milanesi, O.; Gregori, D.; Stellin, G. The natural history and surgical outcome of patients with scimitar syndrome: a multi-centre European study. Eur. Heart J. [Internet] 2017, 39(12), 1002–11. [Google Scholar] [CrossRef] [PubMed]
- Karthekeyan, R.B.; Saldanha, R.; Sahadevan, M.R.; Rao, S.K.; Vakamudi, M.; Rajagopal, B.K. Scimitar Syndrome: Experience with 6 Patients. Asian Cardiovasc. Thorac. Ann. 2009, 17(3), 266–71. [Google Scholar] [CrossRef] [PubMed]
- Albinni, S.; Marx, M.; Lang, I. Focused Update on Pulmonary Hypertension in Children—Selected Topics of Interest for the Adult Cardiologist. Medicina-lithuania 2020, 56(9), 420–0. [Google Scholar] [CrossRef] [PubMed]
- Trimech, T.; Ajlani, B.; Cohen, S.; Chérif, G.; Chavelas, C.; Nistor, M.; et al. Scimitar syndrome with bicuspid aortic valve. A case report of cross-sectional non- invasive imaging allowing a complete anatomical and functional assessment. Ann. De Cardiol. Et. d’Angéiologie [Internet] 2020, 69(5), 317–22. [Google Scholar] [CrossRef] [PubMed]
- Ngai, C.; Freedberg, R.S.; Latson, L.; Argilla, M.; Benenstein, R.J.; Vainrib, A.F.; et al. Multimodality imaging of scimitar syndrome in adults: A report of four cases. Echocardiography 2018, 35(10), 1684–91. [Google Scholar] [CrossRef] [PubMed]
- Shinohara, G.; Morita, K.; Uno, Y.; Yamashiro, M.; Hashimoto, K. Scimitar syndrome in an infant with right lung hypoplasia, ventricular septal defect, and severe pulmonary hypertension. General. Thorac. Cardiovasc. Surg. 2010, 58(10), 524–7. [Google Scholar] [CrossRef] [PubMed]
- Han, F.; Kiparizoska, S.; Campbell, W.; Richards, C.; Kogon, B.; Holloway, M.; et al. The case of the missing pulmonary vein: A focused update on anomalous pulmonary venous connection in congenital cardiovascular disease. Echocardiography 2019, 36(10), 1930–5. [Google Scholar] [CrossRef] [PubMed]
- Jacquemyn, X.; Van De Bruaene, A.; Budts, W.; Dresselaers, T.; Bogaert, J. Anatomy vs. shunt fraction: haemodynamic consequences in atrial septal defects and partial anomalous pulmonary venous connection—a comprehensive CMR study. Eur. Heart Journal—Cardiovascular Imaging 2025. [Google Scholar] [CrossRef] [PubMed]
- Seller, N.; Yoo, S.J.; Grant, B.; Grosse-Wortmann, L. How many versus how much: comprehensive haemodynamic evaluation of partial anomalous pulmonary venous connection by cardiac MRI. Eur. Radiol. 2018, 28(11), 4598–606. [Google Scholar] [CrossRef] [PubMed]
- Cacciapuoti, F.; Mauro, C.; Crispo, S.; Carpinella, G.; Volpicelli, M. The Long Shadow of Repair: Late-Onset Atrioventricular Block and Atrial Arrhythmias After Scimitar Syndrome and Mitral Annuloplasty. Rep. — Med. Cases Images Videos 2025, 8(2), 72–2. [Google Scholar] [CrossRef] [PubMed]
- Yadav, R.; Sharma, A.; Pathak, S. Successful Surgical Management of Incidentally Diagnosed Scimitar Syndrome With Anomalous Connection of the Left Hepatic Vein to Coronary Sinus and Persistent Left Superior Vena Cava. Cureus 2023. [Google Scholar] [CrossRef] [PubMed]
- Samarawickrama, T.; Wijesinghe, N.; Karunarathna, S.; Biyanwila, A. Scimitar syndrome with large atrial septal defect and a rare partial anomalous venous drainage in an adult: a case report. Eur. Heart Journal—Case Rep. [Internet] 2023. [Google Scholar] [CrossRef] [PubMed]
- Aristizabal, A.M.; Guzmán-Serrano, C.A.; Mondol-Villamil, N.V.; Bolaños-Vallejo, L.M.; Mejia-Quiñones, V.; Recio-Gómez, M.A.; et al. Clinical characteristics, imaging findings, management, and outcomes of patients with scimitar syndrome at a tertiary referral healthcare center in Colombia. 18 Apr 2024. [CrossRef] [PubMed]
- Masrani, A.; McWilliams, S.; Bhalla, S.; Woodard, P.K. Anatomical associations and radiological characteristics of Scimitar syndrome on CT and MR. J. Cardiovasc. Comput. Tomogr. 2018, 12(4), 286–9. [Google Scholar] [CrossRef] [PubMed]
- Ielasi, A.; Latib, A.; Agricola, E.; Montorfano, M.; Colombo, A. Scimitar syndrome. J. Cardiovasc. Med. 2011, 12(3), 176–7. [Google Scholar] [CrossRef] [PubMed]
- Geggel, R.L.; Gauvreau, K.; Callahan, R.; Feins, E.N.; Baird, C.W. Scimitar syndrome: A new multipatch technique and incidence of postoperative pulmonary vein obstruction. JTCVS Tech. 2020, 4, 208–16. [Google Scholar] [CrossRef] [PubMed]
- Cheng, W.; Li, Z.; Zhu, Y.; Ding, N.; Yan, D.; Yi, H. Surgical correction for scimitar syndrome by right thoracotomy and direct anastomosis in children. Pediatr. Investig. 2021, 5(1), 46–51. [Google Scholar] [CrossRef] [PubMed]
- Cruz-Galbán, A.; Ruiz-Cantador, J.; Elvira González-García, A. Atypical presentation of scimitar syndrome with severe hepatomegaly: a case report. Oxf. Acad. Eur. Heart Journal—Case Rep. 2021. [Google Scholar] [CrossRef] [PubMed]
- Buz, S.; Alexi-Meskishvili, V.; Villavicencio-Lorini, F.; Yigitbasi, M.; Hübler, M.; Weng, Y.; et al. Analysis of Arrhythmias After Correction of Partial Anomalous Pulmonary Venous Connection. Sci. Ann. Thorac. Surg. 2009. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Diagram of study selection using PRISMA flow design.
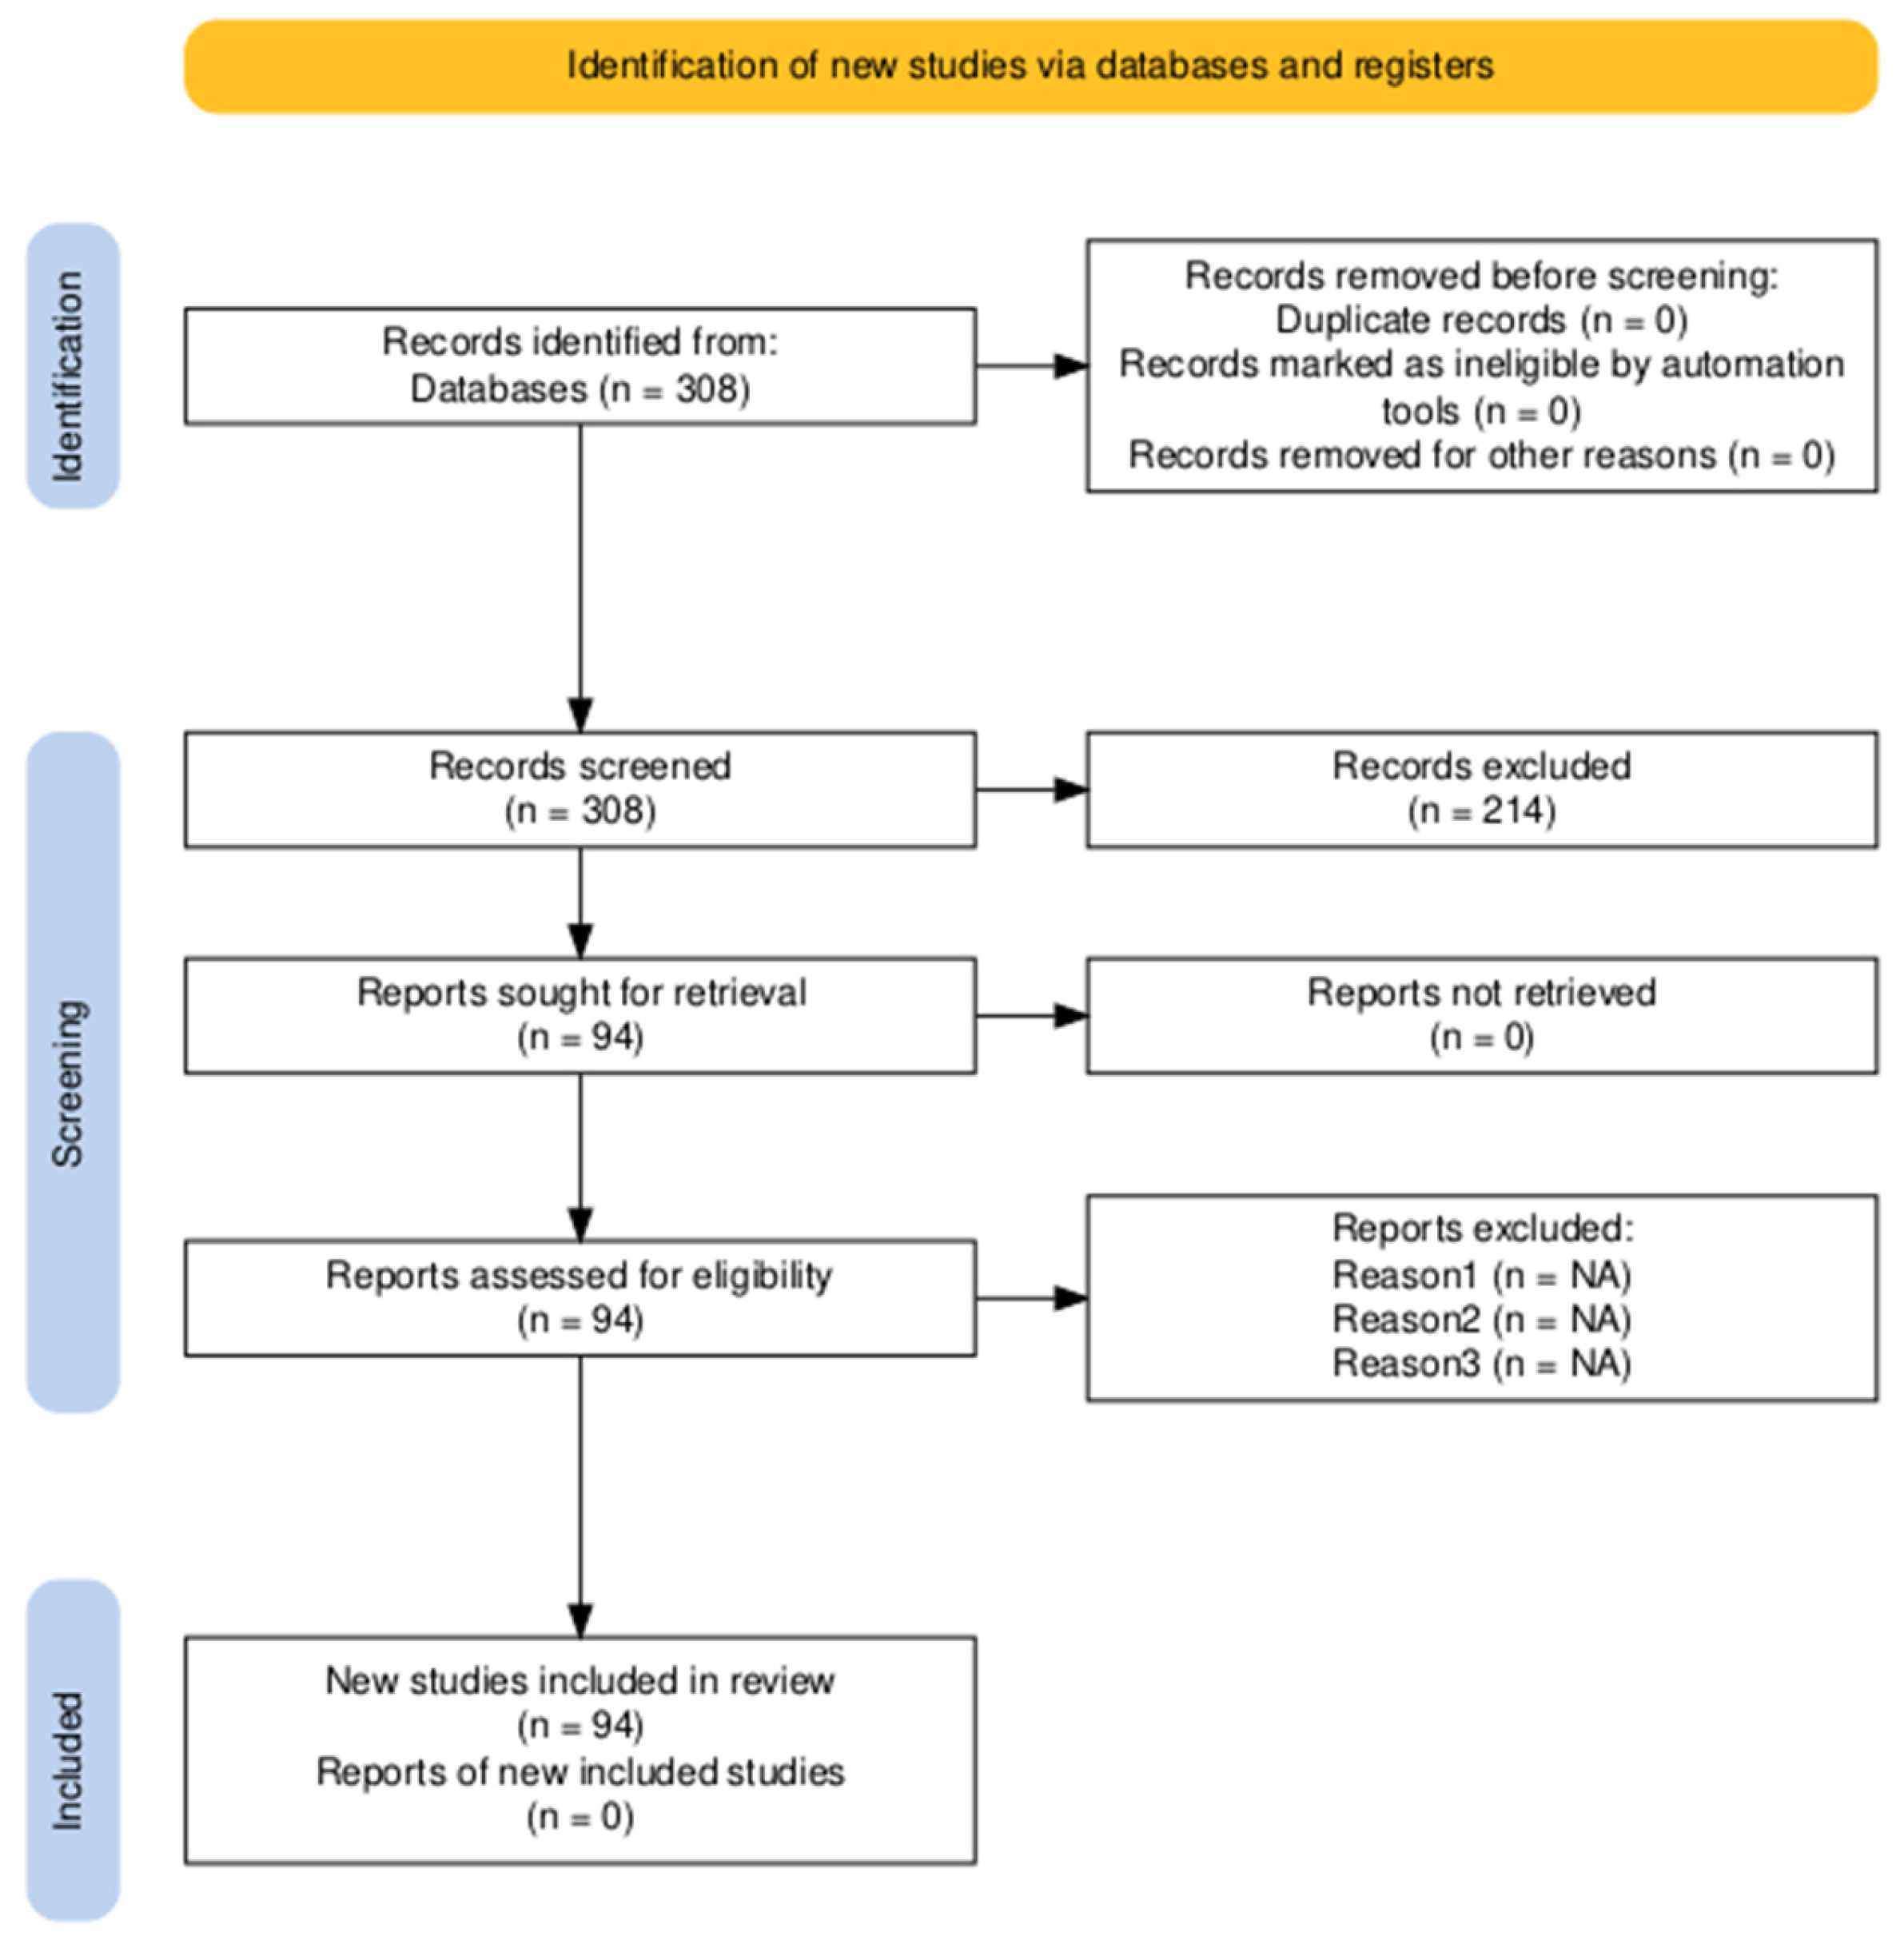

Table 1.
Inclusion and Exclusion criteria of the articles that underwent initial screening.
| Inclusion Criteria | Exclusion Criteria |
|---|---|
| Human patients with confirmed Scimitar syndrome | Animal studies |
| Reported atrial or supraventricular arrhythmias | Narrative/literature reviews |
| Primary studies: case reports, case series, RCTs | Non-English publications |
| All age groups (Pediatrics and Adults) | Abstract-only publications |
| Published between 2008-2026 |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.