

Submitted:
22 February 2026
Posted:
23 February 2026
You are already at the latest version
Abstract
Background/Objectives: Intraoperative methadone has emerged as a significant pharmacological strategy in cardiac surgery to improve postoperative analgesic outcomes and reduce the reliance on rescue short action opioids. This review aims to synthesize evidence regarding the safety and efficacy of intravenous methadone compared to other strategies for postoperative pain control in adult and pediatric cardiac surgeries. Methods: This scoping review relied on electronic searches in PubMed, Web of Science, Cochrane Library, and EMBASE up to January 2026. From 199 articles retrieved, 41 were included, focusing on analgesic efficacy, safety, pharmacokinetic variations during cardiopulmonary bypass (CPB), and cost-effectiveness. Results: The implementation of methadone results in a 30% to 70% reduction in postoperative opioid requirements. Patients experience significantly lower pain scores from 24 to 72 hours and a 20% to 30% improvement in satisfaction regarding their recovery. In pediatric populations (neonates and children), the use of methadone leads to a significant reduction in opioid needs and a high rate of extubation in the operating room. Pharmacokinetically, a 48% drop in methadone concentration occurs during CPB due to hemodilution and sequestration. Safety data confirms that intraoperative use does not prolong mechanical ventilation; however, doses exceeding 0.25 mg/kg are linked to an increased incidence of delirium. Economically, optimized recovery generates savings of up to $6,355 per patient within seven days. Conclusions: Intraoperative methadone is a robust and safe analgesic option for cardiac surgery, including pediatric cases. It offers profound opioid-sparing effects and significant cost reductions, if dosages are carefully managed to minimize delirium risks.
Keywords:
methadone
; cardiac surgical procedures
; postoperative pain
; pharmacokinetics
1. Introduction
Acute postoperative pain commonly affects patients after cardiac surgery, particularly during the first 48 hours following the operation, and often presents with moderate to severe intensity [1]. This pain substantially hinders recovery, adversely affecting mobility, pulmonary function, and overall quality of life [2]. Therefore, achieving effective postoperative analgesia is essential to mitigate these negative outcomes and accelerate recovery [3]. Opioids have traditionally the cornerstone of perioperative analgesia for cardiac surgery patients, both during and after surgery, despite increasing awareness of dependence risks and other long-term harms [4]. While opioids provide excellent pain relief, their adverse effects — such as respiratory depression, nausea, and vomiting — can extend mechanical ventilation and slow recovery [5]. As a result, developing multimodal analgesic approaches that reduce opioid exposure while preserving pain control has become a central objective in contemporary practice [6]. Multiple studies have evaluated combinations of agents like dexamethasone, gabapentin, ibuprofen, and paracetamol to diminish postoperative opioid requirements after cardiac procedures [7]. Nevertheless, opioid therapy remains a key element of postoperative analgesia in cardiac surgery [4].
In this scenario, methadone emerges as a promising alternative due to its unique pharmacokinetic and pharmacodynamic profile, which includes a long half-life that can reach up to 72 hours depending on the dose, and action on multiple opioid receptors [8]. Concurrently, plasma concentrations of methadone after intravenous administration equilibrate rapidly with the site of effect, with a t1/2 ke0 of 4 minutes [8]. Its application as a single intravenous dose during anesthesia induction has demonstrated provision of rapid and prolonged pain relief, which can mitigate both acute postoperative pain and chronic pain in patients undergoing cardiac surgery (Figure 1) [8,9]. Furthermore, methadone has a mechanism of action that extends to the blockade of N-methyl-D-aspartate receptors, conferring additional properties that may attenuate central sensitization and opioid tolerance [9]. Inhibition of serotonin and norepinephrine reuptake also contributes to its robust analgesic profile, significantly differentiating it from morphine, which primarily acts on µ opioid receptors [9]. This pharmacological difference suggests that methadone may offer superior analgesia with a potentially more favourable adverse effect profile compared to morphine or other short-acting opioids leading to fewer adverse effects and promoting multimodal analgesia [4].
The objective of this review is to synthesize the current evidence regarding the safety and efficacy of intravenous methadone compared to other strategies such as intravenous morphine or other short-acting opioids and even different techniques in controlling postoperative pain in patients undergoing cardiac surgeries, both in adult and pediatric populations, addressing aspects such as opioid consumption, mechanical ventilation time, patient satisfaction, financial impact, and incidence of adverse events.
2. Materials and Methods
Electronic search was conducted in four research databases: PubMed, Web of Science, Cochrane Library, and EMBASE. The literature search was completed on January 10, 2026. The search terms, including Boolean operators, were as follows:
PubMed:
- intraoperative methadone AND cardiac surgery [All Fields]
- (“Cardiac Surgical Procedures”[Mesh]) AND “Methadone”[Mesh]
- Web of Science:
- Methadone AND Cardiac surgery (All fields)
- Methadone AND (Cardiac surgery OR Heart Surgery)
- EMBASE:
- (‘intraoperative methadone’ OR (intraoperative AND (‘methadone’/exp OR methadone))) AND (‘heart surgery’/exp OR ‘heart surgery’)
- Cochrane Library
- Methadone in Record Title AND “cardiac-surgery” in Record Title—(Word variations have been searched)
A manual search of references was also performed. All studies evaluating the use of intraoperative methadone in patients of any age range undergoing open or minimally invasive cardiac surgery were included. This strategy included randomized clinical trials, observational studies, editorials, and review articles. The articles were independently reviewed by two authors in parallel (IRR and AJP), with discrepancies resolved by the senior author (JPJP). Congress abstracts, case reports, and manuscripts in languages other than English were excluded from the review.
3. Results
After the search, a total of 199 articles were retrieved. After removing duplicates, 41 articles from the literature were included, focusing on the main outcomes related to the analgesic efficacy, safety, and clinical impacts of methadone compared to other medications or techniques in the context of cardiac surgery. The search strategy flowchart is detailed in Figure 2.
All observational studies and clinical trials in the adult population available up to the time of this literature review are listed in Table 1. The observational studies and clinical trials that studied intraoperative methadone in pediatric cardiac surgery are listed in Table 2. The remaining review articles, post-hoc analysis of the already published clinical studies, editorials, and consensus were used to further discuss the findings from these main articles.
4. Discussion
4.1. Methadone Dose, Timing of Administration, and Influence of Cardiopulmonary Bypass (CPB)
The doses of methadone used intraoperatively in cardiac surgery for postoperative analgesia range between 0.1 mg/kg and 0.3 mg/kg intravenously [22,27,28], generally administered as a single dose based on the patient’s actual body weight. The most frequently studied and used dose in randomized clinical trials is 0.2 mg/kg or 0.3 mg/kg IV. In some protocols, there is an absolute maximum limit of 20 mg per dose.
These doses are typically administered after anesthetic induction and before surgical incision, aiming to establish therapeutic plasma levels before the initial painful stimulus [16]. However, Carvalho et al. administered intravenous methadone at the end of anesthesia compared to intravenous morphine, being superior in analgesia in myocardial revascularization surgeries [12].
The behaviour of methadone plasma concentration can be altered due to hemodilution and changes in blood flow during CPB, which may impact its distribution and elimination, and consequently its analgesic efficacy and safety profile [19]. The study by Salas et al. demonstrated an average 48% drop in methadone concentrations during CPB [19]. Specifically, mean methadone concentrations dropped from 34.8 ng/mL to 18.2 ng/mL after 60 minutes of CPB [19]. This decrease is attributed to hemodilution and drug sequestration in the CPB circuit components [19]. Likewise, the study by Wong et al. observed a significant drop in methadone plasma levels after the start of CPB, resulting in a 37% decrease in methadone plasma concentration [22]. They noted that mean methadone concentrations were 51 ng/mL before CPB and 32 ng/mL after the end of CPB [22].
These findings highlight the need to adjust the dosage or consider supplemental administration strategies to maintain methadone’s analgesic efficacy in patients undergoing CPB, ensuring optimized postoperative pain control [19]. A proposed strategy to compensate this phenomenon is the administration of a supplemental bolus dose of 0.05 mg/kg after the end of CPB, as suggested by some studies, to restore therapeutic plasma levels and optimize postoperative analgesia (Figure 3) [19], as according to the authors, plasma concentrations at the end of surgery would be below the range for effective analgesia, which is suggested to be around 30 to 80 ng/mL. However, with the same dose of 0.2 mg/kg, Wong et al. demonstrated that methadone concentrations, despite decreasing during CPB, remained above the minimum effective analgesic concentration of 30 ng/mL for approximately 24 hours after administration [22]. Therefore, the supplementary methadone dose is still contentious.
4.2. Postoperative Pain Scores
The comparative analysis between methadone and intravenous morphine has demonstrated that methadone provides superior analgesic control [22], resulting in significantly lower pain scores in the first 24 to 72 hours after tracheal extubation [11]. This improvement in pain control is attributed, in part, to methadone’s pharmacological profile, which a long elimination half-life and action on NMDA receptors, contributing to more stable and prolonged analgesia [8,9]. Studies reveal that patients treated with methadone exhibit a reduction in postoperative pain scores that can range from 2 to 3 points on a 10-point numerical pain scale, compared to control groups receiving morphine or other opioids [11,29]. For example, a randomized controlled trial found that mean numerical pain scale scores in the methadone group decreased from 1.28 at 15 minutes post-extubation to 0.55 at 72 hours, while in the morphine group, the reduction was from 3.52 to 1.27 over the same period [22]. Additionally, another clinical trial showed 22% higher efficacy of patients receiving intraoperative methadone than morphine as it yielded a number-needed-to-treat (NNT) score of 6 of satisfactory analgesia in the first 36 hours [12]. This consistency in findings across different study designs reinforces methadone’s efficacy in optimizing postoperative pain management in cardiac surgeries, evidencing its potential to improve patient comfort [4].
In long-term follow-up, patients in the methadone group in cardiac surgeries reported significantly lower frequency of postsurgical pain at 1 month (median score 0) than it was in patients randomized to receive fentanyl (median score 2 [twice per week], P = 0.004) [30]. However, after the first month, no significant differences in pain were observed between the methadone and fentanyl groups at 3, 6, or 12 months post-surgery [30].
In minimally invasive techniques, such as robotic cardiac surgery, intravenous methadone before surgical incision also showed an impact on reducing the risk of severe postoperative pain, reflecting a lower need for opioids in the first 24 postoperative hours [13].
4.3. Postoperative Opioid Consumption
In regards to postoperative opioid consumption in the first days after cardiac surgery, intravenous methadone has demonstrated a significant effect in reducing the need for short-acting opioid rescue doses [4]. Various studies corroborate that intraoperative methadone administration results in a substantial decrease in total morphine equivalent consumption in the first 24 to 48 hours, with reductions ranging from 30% to 70% compared to standard protocols [16,22]. For example, a retrospective study in cardiac surgery demonstrated that intraoperative methadone led to a relative reduction of 44% in morphine equivalent needs in the first 24 postoperative hours, although this difference was not maintained beyond that period [14]. Another large retrospective study indicated that the reduction in opioid consumption was more prolonged with lower opioid utilization in the first 6 postoperative days without compromising pain control [16].
Clinical trials using methadone also showed a marked reduction in postoperative opioid consumption. Wong et al., in a recent clinical trial, evidenced a significant reduction in postoperative morphine needs, with a 63% decrease at 24 hours and 69% up to 72 hours, in addition to a longer time to the first morphine rescue dose for patients who received methadone [22]. In another clinical trial, intraoperative methadone led to a 43% reduction in total intravenous morphine needs in the first 3 postoperative days [11]. Another clinical trial revealed that patients receiving methadone intraoperatively required significantly less rescue morphine (29%) than the morphine group (43%) (p = 0.002) [12].
In a secondary analysis, Milam et al. demonstrated that higher methadone doses (> 0.25mg/kg) were associated with more significant reductions in average pain scores and total morphine equivalent consumption in the first postoperative days, compared to the no-methadone group and lower doses (< 0.25 mg/kg) [18]. In this study, all methadone dosages significantly prolonged the time to first postoperative opioid need, with higher doses showing a more pronounced effect. Benefits in pain reduction and opioid consumption were observed for several days, although they tended to diminish after Day 4 or Day 5 for total morphine equivalents consumption. Lower doses also demonstrated benefits, but generally to a lesser magnitude compared to higher doses, especially in more immediate pain and opioid consumption outcomes [18].
4.4. Patient Satisfaction
Objective measures of patient satisfaction indicate that methadone enhances the postoperative recovery experience after cardiac surgery compared with morphine in several domains, including a higher proportion of patients reporting excellent pain control [12]. This better pain experience contributes to a quicker, less distressing recovery and manifests in higher overall satisfaction scores [12]. The improvement in satisfaction is generally in the 20%–30% range versus morphine-based protocols, with patients often describing better sleep and fewer adverse effects [32].
4.5. Postoperative Nausea and Vomiting (PONV)
Regarding PONV in cardiac surgery, methadone has demonstrated a comparable or even lower incidence of gastrointestinal adverse events compared to morphine, despite its prolonged half-life [27]. Some studies suggest that methadone may have a more favourable gastrointestinal safety profile, resulting in less need for antiemetics and a more comfortable recovery [11]. The absence of significant differences in opioid-related adverse effects, including nausea and vomiting, within 72 hours after cardiac surgery reinforces methadone’s safety profile [22]. The study by Edwards et al. also found no increase in the incidence of PONV with methadone use, even when compared to its non-administration [16]. The study by Udelsmann et al. found that methadone may even reduce the incidence of PONV compared to morphine or placebo [10].
4.6. Respiratory Depression and Mechanical Ventilation Time
One of the main concerns related to intraoperative methadone use, due to its prolonged half-life of 24-36 hours, is the potential for respiratory depression or prolongation of mechanical ventilation time. Serum methadone concentrations for respiratory depression must be above 100 ng/ml, which occurs for a few minutes after its intravenous administration [8,9]. However, current literature does not support this concern, with various studies demonstrating that intraoperative methadone in cardiac surgeries does not significantly prolong extubation time or mechanical ventilation duration compared to other opioids [12,22]. Recent systematic review indicates methadone’s safety in this regard, showing no link to increased hypoventilation, hypoxemia, or need for extended ventilatory support within 24 hours postoperatively [4]. Rates of respiratory complications, including hypoxia, do not significantly differ between methadone and fentanyl groups [4,31].
4.7. QT Interval Prolongation
A significant concern with methadone use, especially at higher doses or in patients with cardiac comorbidities, is the potential to prolong the QT interval, which may increase the risk of severe ventricular arrhythmias, such as Torsades de Pointes [32]. This effect of methadone occurs through inhibition of HERG channels, which theoretically can lead to long QT syndrome [33]. A large retrospective study specifically evaluating QTc interval demonstrated that a single intraoperative methadone administration did not prolong QTc nor increase the incidence of postoperative arrhythmias in adults undergoing cardiac surgery. A modest and transient QTc prolongation was observed immediately after surgery, which normalized within 24 hours, both in methadone and control groups. Additionally, there were no significant differences in ventricular or atrial arrhythmias, nor in 30-day or 1-year mortality between groups [33]. The study also highlights that other common perioperative medications, such as fentanyl and ondansetron, can cause QT interval prolongation and have additive effects [33]. The study by Edwards et al. also investigated QTc changes, concluding that the QTc change in the group receiving only methadone was not statistically different from the change in the group not receiving methadone. Interestingly, the group receiving methadone along with other opioids showed a decrease in QTc after surgery compared to before surgery [16].
4.8. Postoperative Delirium
Although delirium after cardiac surgery is a common, multifactorial complication, most studies of intraoperative methadone have not consistently shown an increased delirium incidence versus other analgesic strategies. However, one retrospective cohort study found that higher methadone doses (>0.25 mg/kg) were associated with a significantly greater risk of postoperative delirium compared with lower doses (<0.25 mg/kg) [18]. Thus, careful dose selection is essential to mitigate delirium risk, particularly in vulnerable patients.
4.9. Methadone as an Opioid-Sparing Strategy in Multimodal Analgesia
Despite being an opioid, methadone stands out for its ability to act as a strategy to spare other short-acting opioids [34]. This is attributed, in part, to its long half-life and versatile mechanism of action, which includes NMDA receptor antagonism and inhibition of neurotransmitter reuptake, contributing to more sustained analgesia and reducing opioid-induced hyperalgesia [9,32]. Considering methadone in multimodal analgesia, a recent retrospective study in adults undergoing cardiac surgery compared three regimens: opioid-only, multimodal 1, and multimodal 2. The multimodal regimens, especially the one with methadone and dexmedetomidine, significantly reduced total opioid consumption before hospital discharge [35]. Another recent study comparing methadone alone with the combination of methadone and ketamine demonstrated that the methadone-ketamine combination prolonged the time to first postoperative opioid administration and reduced total opioid consumption on the first day, indicating an additional benefit in early opioid consumption reduction; however, the combination did not show additional benefits regarding pain scores or other complications beyond the immediate postoperative period [15].
Another observational study assessing methadone as a component of a multimodal strategy, in combination with magnesium, ketamine, lidocaine, and dexmedetomidine, by Weinberg et al., found a 35% reduction in total mechanical ventilation time compared to the usual care group. Additionally, 40.2% were extubated within 4 hours, versus 11.4% in the control group. In addition to respiratory benefits, the multimodal strategy provided patients with lower pain intensity in the first 24 postoperative hours, with a maximum score of 4, versus 6 in the usual care group. In parallel, there was lower morphine equivalent consumption in the first 24 and 48 postoperative hours. Furthermore, the multimodal protocol did not increase risks of adverse events, reintubations, or critical care unit readmissions, and there was no respiratory depression requiring naloxone or reintubation in any group [21]. It is important to emphasize that the study evaluated the combination of medications within a multimodal protocol compared to the traditional opioid-based protocol, not the isolated use of methadone. In this context, methadone contributed to enhanced postoperative analgesia and opioid use reduction, highlighting its opioid-sparing property [21].
When compared to traditional techniques used for postoperative analgesia, such as intrathecal morphine, intravenous methadone proved to be a comparable option in terms of opioid consumption, with no significant difference in opioid consumption measured as oral morphine equivalents, despite intrathecal morphine showing a marginal mean effect of 0.49 in reducing immediate postoperative pain scores. This study reinforces methadone as a valuable alternative in postoperative pain management in cardiac surgery within an ERAS protocol, mainly due to concerns regarding coagulation changes inherent to heparinization during CPB and the risk of spinal hematoma associated with neuraxial techniques [17].
A small clinical pilot trial showed that even when given orally at 0.3 mg/kg in preoperative setting, just before operation theatre admission, methadone may be a valuable strategy in the context of multimodal analgesia, reducing significantly the opioid consumption in the first 24 hours when compared to placebo without increasing adverse effects, serving as a simple opioid sparing technique [36].
In light of the growing evidence, methadone administration is recognized and recommended in the Enhanced Recovery After Surgery context for cardiac surgery as a strategy that contributes to multimodal analgesia, aiming to reduce total opioid consumption, decrease postoperative pain intensity, and consequently optimize patient recovery [29,37].
4.10. Methadone in Pediatric Cardiac Surgery
Although most research focuses on adults, intravenous methadone has also been explored in pediatric cardiac surgeries, presenting a distinct pharmacokinetic and pharmacodynamic profile that requires specific considerations for this population. The doses reported in pediatric cardiac surgery are variable. In one study, the dosage used was 0.1 mg/kg in increments at induction, incision, and start of cardiopulmonary bypass, with the total intraoperative dose not exceeding 0.4 mg/kg [24]. Another study used a mean methadone dose of 0.26 mg/kg [25]. In a specific case, the dose was reduced to 0.15 mg/kg for a patient undergoing a procedure without CPB. In summary, the 0.1 mg/kg intravenous dose is frequently cited as an initial or incremental dose in pediatric protocols [38]. However, the spectrum of doses used can extend up to 0.3 mg/kg as a single dose, or up to 0.4 mg/kg as a total intraoperative dose [24,25].
A recent pharmacokinetic study of intravenous methadone in the pediatric age group suggests an initial dose of 0.1 mg/kg intravenously every 8 hours for pain control in children, with the caveat that titration is essential due to significant individual variability, as the observed median half-life of methadone was 20.5 hours (3.0–86.2 hours) [38]. This wide variability in half-life indicates that the duration of effect may differ significantly among children, reinforcing the need for individualized titration. Dosage recommendations for children under 6 months of age should be interpreted with caution, as the effects of methadone clearance maturation may not have been fully captured by the study model. For pain control, a safety target was established as having less than 10% of simulated individuals with a maximum concentration above 300 ng/mL. The maximum recommended dose is 10 mg per dose [38]. Another pharmacologic study, in adolescents (10-18 years), but in major non-cardiac surgeries, showed that patients who received methadone intraoperatively (0.1 mg/kg, maximum 5 mg) and postoperatively every 12 h for 3-5 doses in a multimodal analgesic protocol resulted in safe and lower blood methadone levels, <100 ng/ml, a threshold previously associated with respiratory depression [39].
Some studies, such as Robinson et al. and Barnett et al., indicate that intraoperative methadone is associated with a significant decrease in opioid use, both intraoperatively and in the first 24-36 postoperative hours, in pediatric patients [23,24]. The study by Robinson et al. indicated that the methadone group consumed approximately 43% to 54% less morphine equivalents per kilogram intraoperatively, in the first 12 hours, and in the first 36 postoperative hours compared to the control group [23]. Similarly, the study by Barnett et al. showed reductions of about 65% in intraoperative opioid dose and 50% in the first 24 postoperative hours in non-neonatal patients, and a 66% intraoperative reduction in neonates in the methadone group [24]. Robinson et al. and Iguidbashian et al. suggest that this methadone presents acceptable safety, without increased incidence of significant adverse events, such as extubation failure, QTc prolongation, or nausea and vomiting, when used intraoperatively in children [23,25].
As part of a multimodal regimen, in association with ketamine, lidocaine, acetaminophen, and parasternal ropivacaine injection, methadone facilitates recovery by promoting early extubation and enhanced recovery. The study observed a high rate of 96% extubation in the operating room in pediatric patients undergoing cardiac surgery, and no reintubation was required [25]. Finally, in older children, intraoperative methadone demonstrated analgesia comparable to non-methadone-based analgesia [26].
However, several limitations must also be considered in the intraoperative use of methadone in the context of pediatric surgery. Most studies are retrospective, cohort studies, or case series. This means there is an inherent risk of biases and confounding factors, limiting the ability to establish strong causality. Additionally, some studies, such as Robinson et al. and Iguidbashian et al., have relatively small samples, which may limit the generalization of results. Furthermore, variations in methadone doses, administration schedules, and the use of multimodal regimens (as in Iguidbashian et al.) make it difficult to isolate the pure effect of methadone and compare directly between studies [23,25]. The study Blasiole et al., for example, suggests that the benefits of methadone may vary with age, with younger children presenting longer hospital stays and higher maximum pain scores in the methadone group [26]. Finally, the studies mainly focus on perioperative outcomes and the first hours/days after surgery, without addressing the long-term impact of methadone on chronic pain or neurological development.
Therefore, future prospective and randomized studies with larger samples are crucial to better elucidate the role of methadone in pediatric cardiac surgeries, noting that the clinical trial Evaluation of Analgesia for Cardiac Elective Surgery in Children (https://clinicaltrials.gov/study/NCT06626035) is still in the recruitment phase.
4.11. Financial Impact
The implementation of intravenous methadone can generate significant savings for the health system by reducing hospital length of stay and costs associated with postoperative complications and high consumption of other more expensive analgesics. These savings are justified by the possibility of earlier discharge and the reduction in the need for treatments for chronic pain, which often result from inadequate management of acute postoperative pain [40]. Additionally, standardizing pain management strategies, including the use of methadone, can optimize hospital resources and improve health system efficiency [41]. A recent study showed that intraoperative methadone use, especially combined with short-acting opioids, is associated with significant reduction in postoperative costs in cardiac surgery. Adjusted mean costs for 7 days were $6,355 higher in the group without methadone compared to the methadone group; on postoperative days 0 and 1, daily costs were significantly higher without methadone. Unadjusted total costs for 7 days were lower in the methadone + other opioids group (M+O) versus methadone alone or only other opioids, with M+O $7,402 lower than the group using opioids other than methadone. These differences mainly stem from lower costs on the surgical day, linked to better pain control and optimized recovery protocols. As a low-cost opioid, methadone balances effective analgesia and limited opioid complications, reducing expenses in cardiovascular care [41].
5. Conclusions
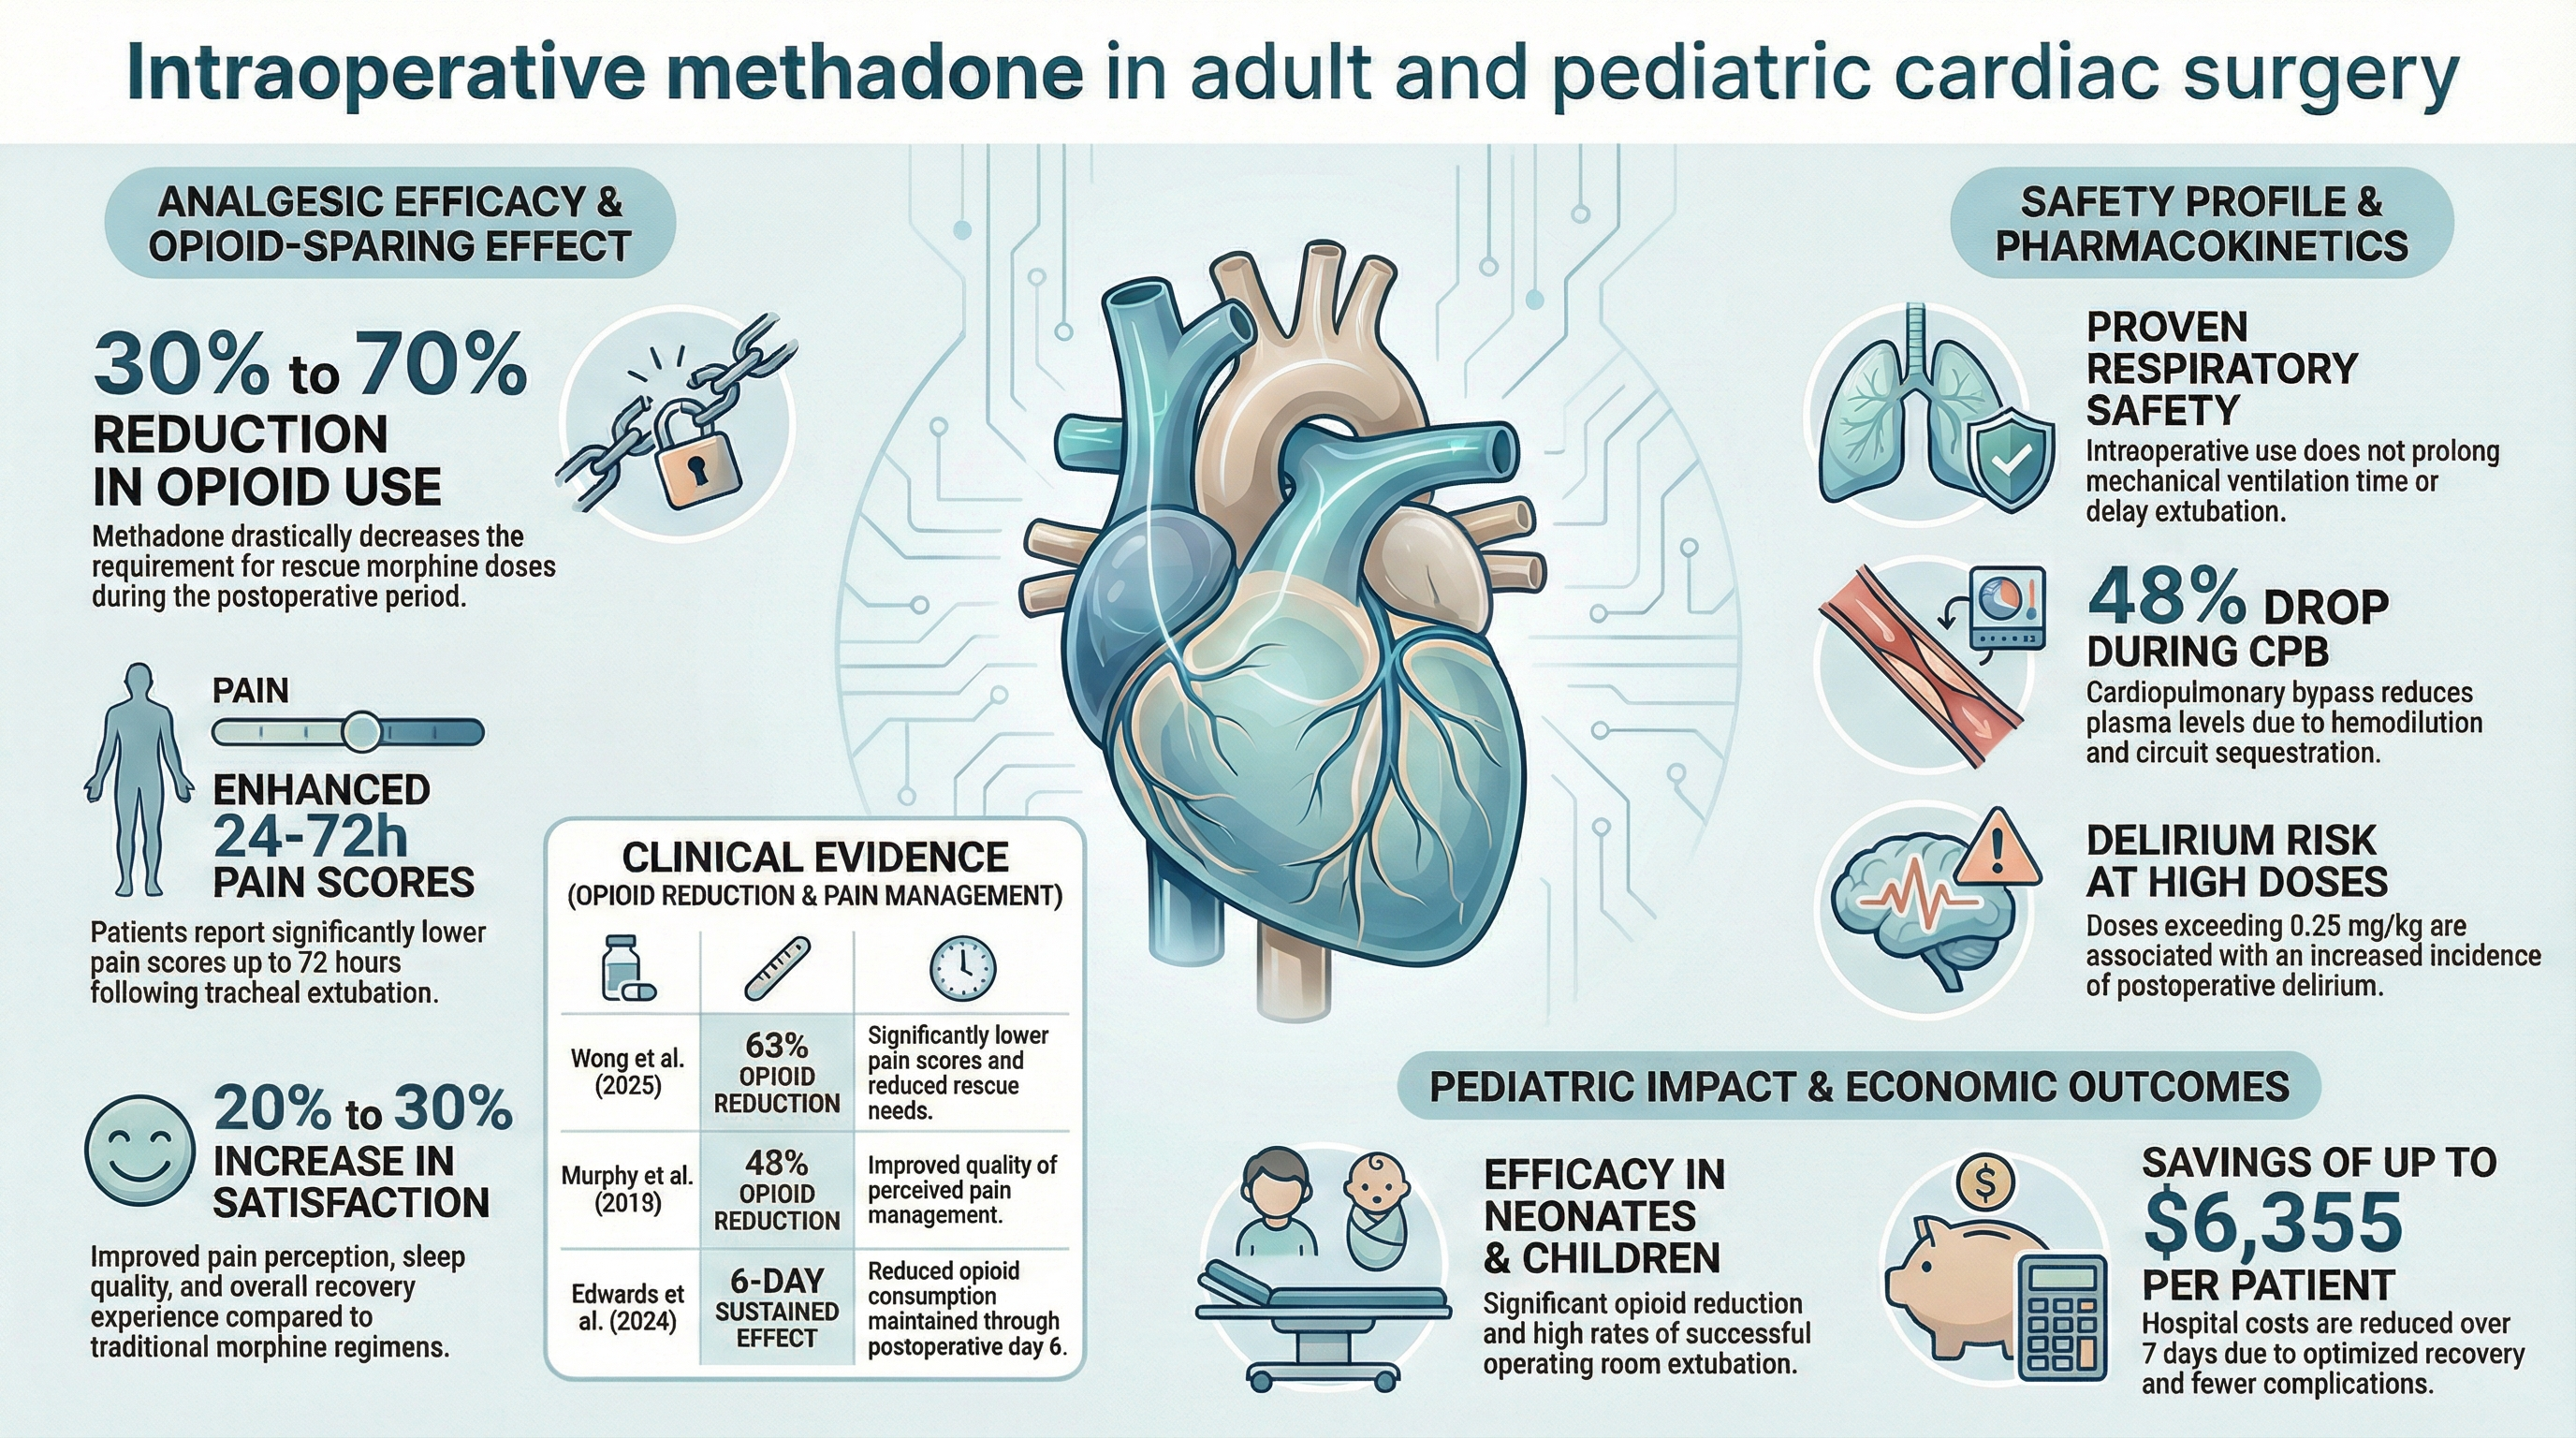
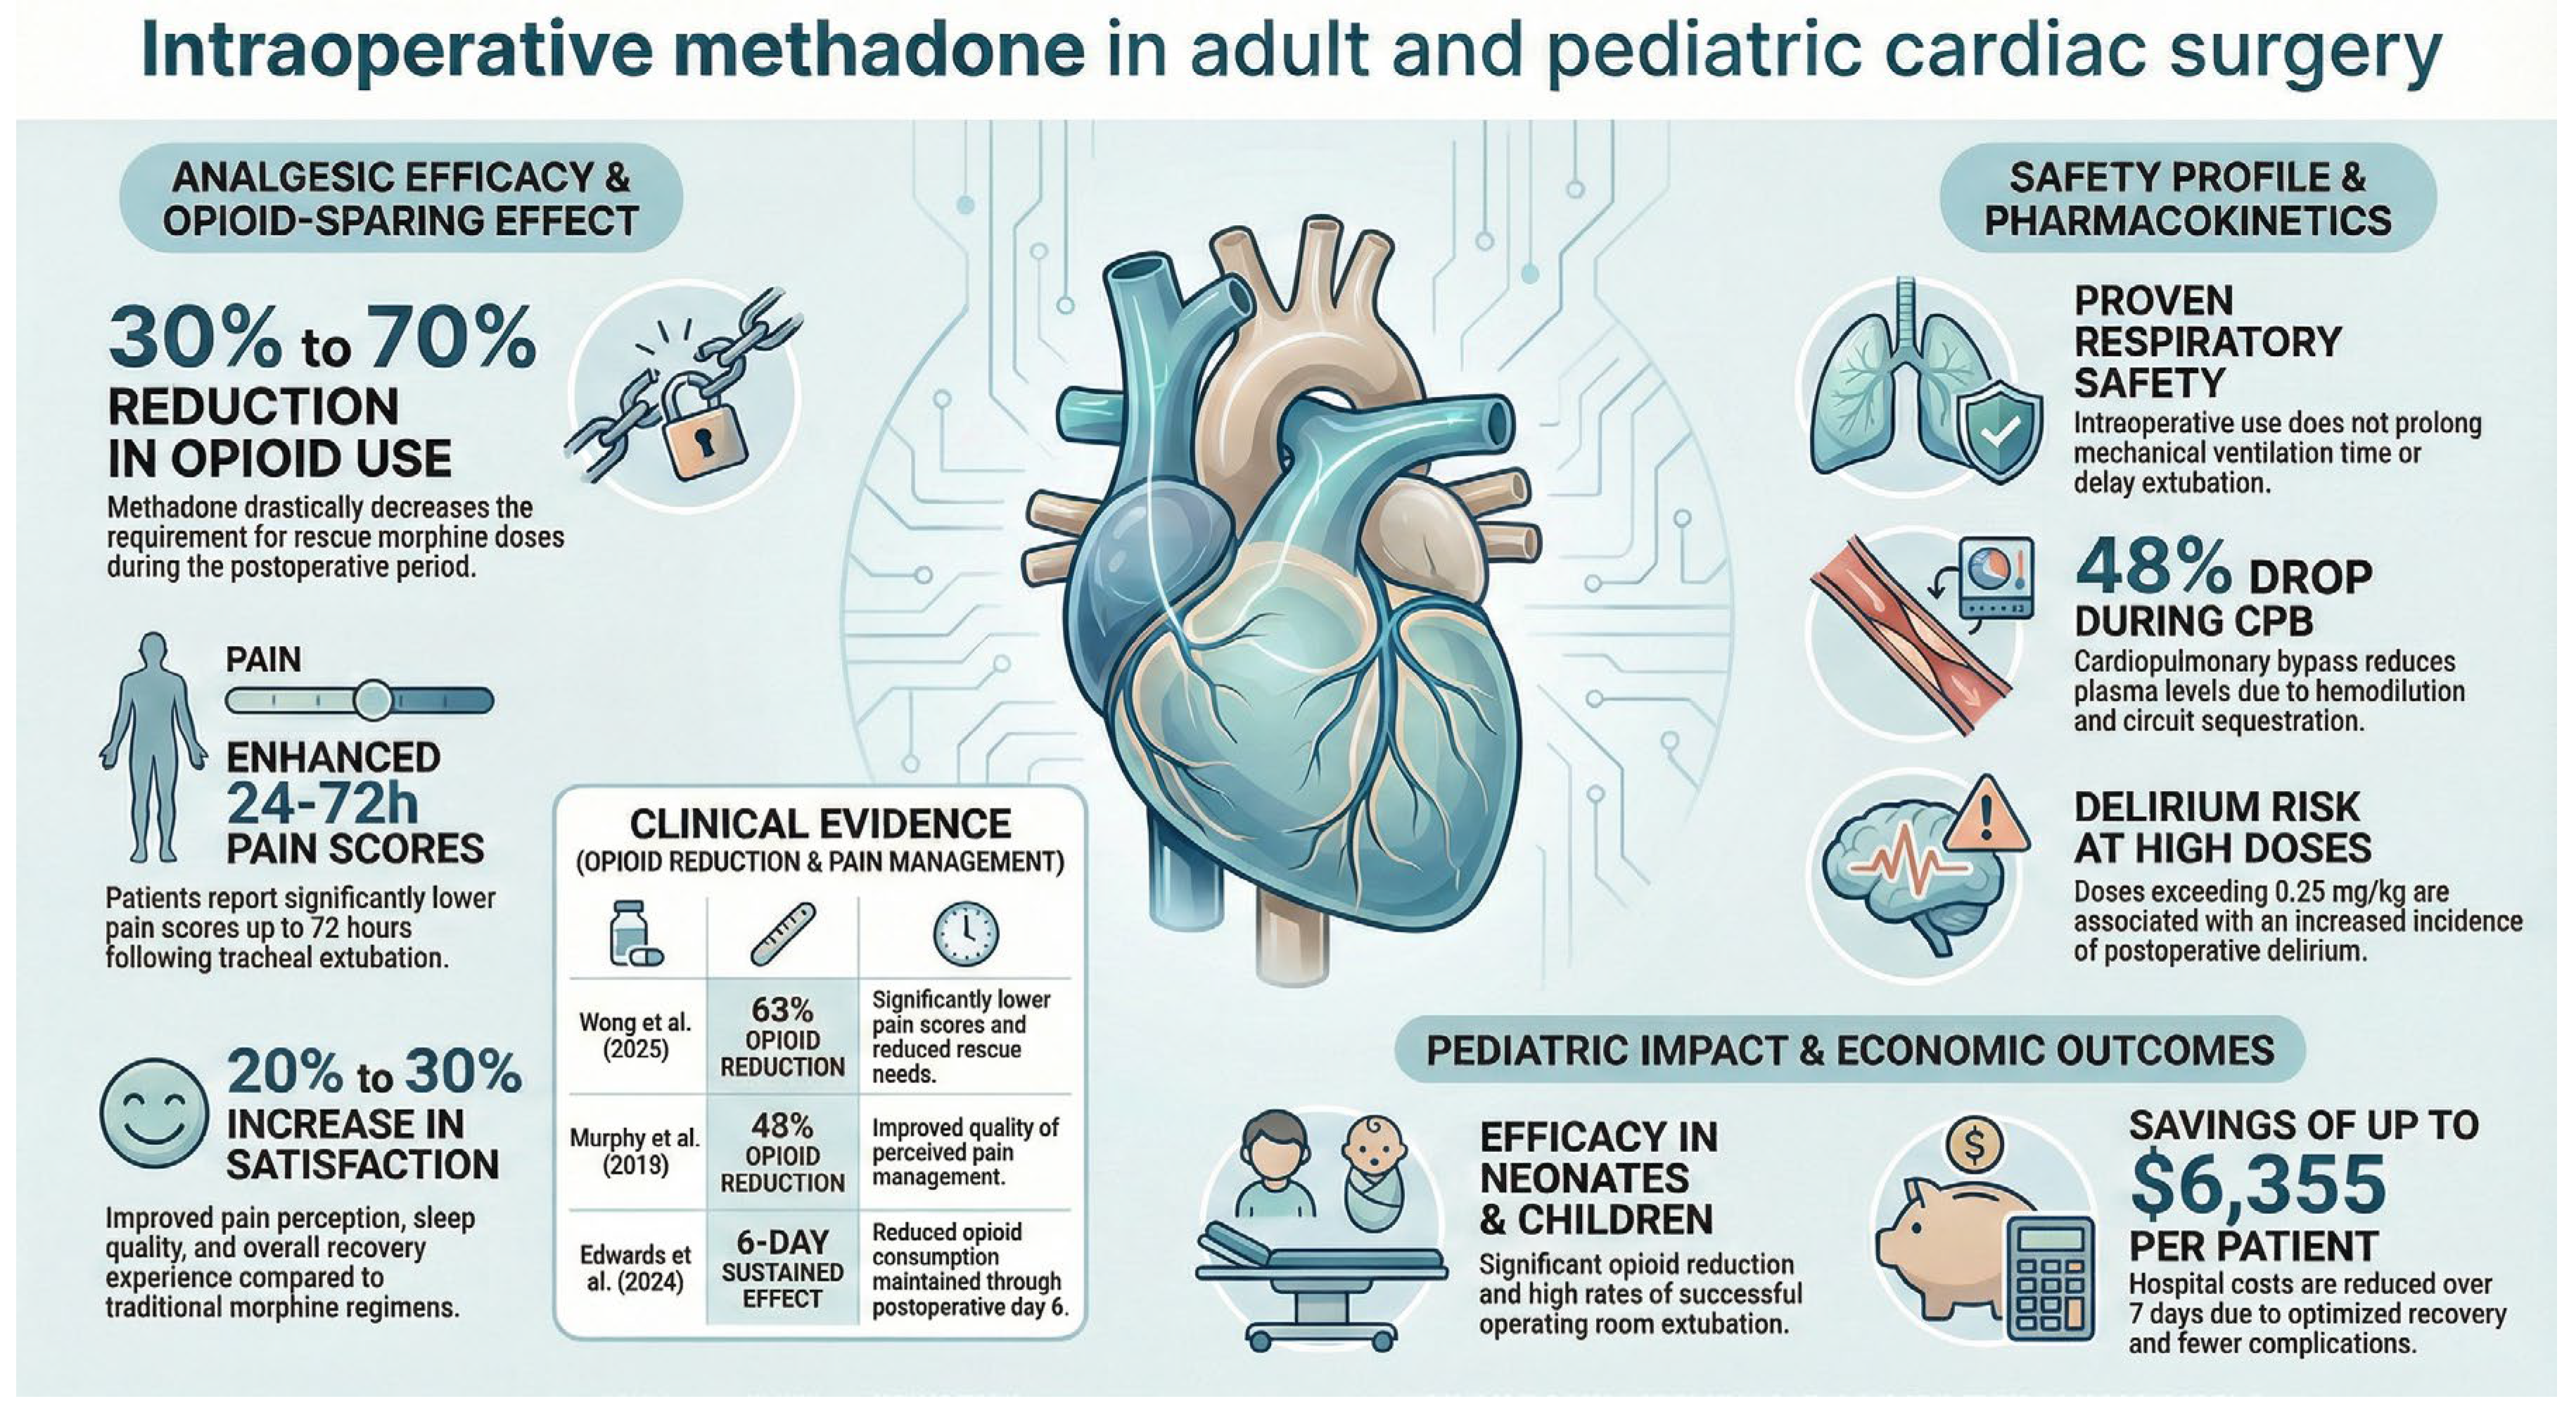
Intravenous methadone represents a meaningful advancement in postoperative pain management for cardiac surgery: it offers superior analgesia, lowers opioid consumption, has an acceptable safety profile, and contributes to more efficient use of healthcare resources, making it a valuable component of ERAS protocol in cardiac surgery (Graphic Abstract). Nevertheless, careful dosing and monitoring for adverse effects — such as delirium and QT prolongation — are essential. Continued research, including larger randomized trials, particularly in pediatric populations, is required to refine dosing recommendations, evaluate novel therapeutic combinations, and determine the long-term effects of methadone on outcomes after cardiac surgery.
Author Contributions
Conceptualization, J.P.J.P. and I.R.R; methodology, J.P.J.P., I.R.R., A.J.P.; writing—original draft preparation, J.P.J.P., I.R.R, C.E.R.B., A.P.G.J.; F.C.P.S.; writing—review and editing, J.P.J.P., I.R.R., A.J.P., N.AM.P.; visualization, J.P.J.P., I.R.R., N.AM.P.; supervision, J.P.J.P.; All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Graphic Abstract.
Graphic abstract summarizing the effects of intraoperative methadone in cardiac surgery both in adults and children.
Graphic Abstract.
Graphic abstract summarizing the effects of intraoperative methadone in cardiac surgery both in adults and children.
References
- Konstantatos, A.; Silvers, A.J.; Myles, P.S. Analgesia Best Practice After Cardiac Surgery. Anesthesiol. Clin. 2008, 26, 591–602. [Google Scholar] [CrossRef] [PubMed]
- Zubrzycki, M.; Liebold, A.; Skrabal, C.; Reinelt, H.; Ziegler, M.; Perdas, E.; Zubrzycka, M. Assessment and pathophysiology of pain in cardiac surgery. J. Pain Res. 2018, ume 11, 1599–1611. [Google Scholar] [CrossRef]
- Wynne, R.; Fredericks, S.; Hyde, E.K.M.; Matthews, S.; Bowden, T.M.; O'Keefe-McCarthy, S.; Martorella, G.P.; Magboo, R.M.; Gjeilo, K.H.; Jedwab, R.M.M.; et al. Multimodal Analgesic Effectiveness on Acute Postoperative Pain Management After Adult Cardiac Surgery: Protocol for a Systematic Review. J. Cardiovasc. Nurs. 2023, 39, E21–E28. [Google Scholar] [CrossRef]
- Goldblatt, J.; Crawford, L.; Ross, J.; Edelman, J.; Pavey, W. The influence of preoperative or intraoperative methadone on postcardiac surgery pain and opioid administration: a systematic review and meta-analysis. Cardiothorac. Surg. 2024, 32, 1–13. [Google Scholar] [CrossRef]
- Pajares, M.; Margarit, J.; García-Camacho, C.; García-Suarez, J.; Mateo, E.; Castaño, M.; Forte, C.L.; Menéndez, J.L.; Gómez, M.; Soto, M.; et al. Vía clínica de recuperación intensificada en cirugía cardiaca. Documento de consenso de la Sociedad Española de Anestesiología, Reanimación y Terapéutica del Dolor (SEDAR), la Sociedad Española de Cirugía Cardiovascular y Endovascular (SECCE) y la Asociación Española de Perfusionistas (AEP). Rev. espanola de Anestesiol. y Reanim. 2021, 68, 183–231. [Google Scholar] [CrossRef]
- Fernandes, R.M.; Pontes, J.P.J.; Borges, C.E.R.; Neto, D.R.d.B.; Pereira, A.d.J.; Carvalho, V.P.; Gomes, L.G.; Silva, F.C.D.P. Multimodal Analgesia Strategies for Cardiac Surgery: A Literature Review. Hearts 2024, 5, 349–364. [Google Scholar] [CrossRef]
- Rafiq, S.; Steinbrüchel, D.A.; Wanscher, M.J.; Andersen, L.W.; Navne, A.; Lilleoer, N.B.; Olsen, P.S. Multimodal analgesia versus traditional opiate based analgesia after cardiac surgery, a randomized controlled trial. J. Cardiothorac. Surg. 2014, 9, 52–52. [Google Scholar] [CrossRef]
- Kharasch, E.D. Intraoperative Methadone: rediscovery, reappraisal, and reinvigoration? Anesthesia Analg. 2011, 112, 13–16. [Google Scholar] [CrossRef]
- Murphy, G.S.; Szokol, J.W. Intraoperative Methadone in Surgical Patients: A Review of Clinical Investigations. Anesthesiology 2019, 131, 678–692. [Google Scholar] [CrossRef]
- Udelsmann, A.; Maciel, F.G.; Servian, D.C.M.; Reis, E.; de Azevedo, T.M.; Melo, M.d.S. Methadone and Morphine during Anesthesia Induction for Cardiac Surgery. Repercussion in Postoperative Analgesia and Prevalence of Nausea and Vomiting. Braz. J. Anesthesiol. 2011, 61, 695–701. [Google Scholar] [CrossRef]
- Murphy, G.S.; Szokol, J.W.; Avram, M.J.; Greenberg, S.B.; Marymont, J.H.; Shear, T.; Parikh, K.N.; Patel, S.S.; Gupta, D.K. Intraoperative Methadone for the Prevention of Postoperative Pain: A Randomized, Double-blinded Clinical Trial in Cardiac Surgical Patient. Anesthesiology 2015, 122, 1112–1122. [Google Scholar] [CrossRef]
- Carvalho, A.C.; Sebold, F.J.G.; Calegari, P.M.G.; Oliveira, B.H.; Schuelter-Trevisol, F. Comparison of postoperative analgesia with methadone versus morphine in cardiac surgery. Brazilian journal of anesthesiology (Elsevier) 2018, 68, 122–127. [Google Scholar] [CrossRef]
- Burtoft, M.A.; Gillespie, S.M.; Laporta, M.L.; Wittwer, E.D.; Schroeder, D.R.; Sprung, J.; Weingarten, T.N. Postoperative Nausea and Vomiting and Pain After Robotic-Assisted Mitral Valve Repair. J. Cardiothorac. Vasc. Anesthesia 2020, 34, 3225–3230. [Google Scholar] [CrossRef]
- Wang, D.J.; Song, P.; Nault, K.M. Impact of intraoperative methadone use on postoperative opioid requirements after cardiac surgery. Am. J. Heal. Pharm. 2021, 79, 636–642. [Google Scholar] [CrossRef]
- Petty, S.A.B.; Raynor, G.; Verdiner, R.; Stephens, E.H.; Oboh, O.; Williams, T.; Shore-Lesserson, L.; Milam, A.J. The Use of Methadone and Ketamine for Intraoperative Pain Management in Cardiac Surgery: A Retrospective Cohort Study. J. Cardiothorac. Vasc. Anesthesia 2024, 39, 414–419. [Google Scholar] [CrossRef] [PubMed]
- Edwards, J.N.; Whitney, M.A.; Smith, B.B.; Fah, M.K.; Petty, S.A.B.; Durra, O.; Sell-Dottin, K.A.; Portner, E.; Wittwer, E.D.; Milam, A.J. The role of methadone in cardiac surgery for management of postoperative pain. BJA Open 2024, 10, 100270. [Google Scholar] [CrossRef] [PubMed]
- LaColla, L.; Nanez, M.A.; Frabitore, S.; Lavage, D.R.; Warraich, N.; Luke, C.; Sultan, I.; Sadhasivam, S.; Subramaniam, K. Intravenous Methadone versus Intrathecal Morphine as Part of an Enhanced Recovery After Cardiac Surgery Protocol on Postoperative Pain and Outcomes: A Retrospective Cohort Study. J. Cardiothorac. Vasc. Anesthesia 2024, 38, 2314–2323. [Google Scholar] [CrossRef] [PubMed]
- Milam, A.J.; Fah, M.K.; Houston, B.T.; Youssef, M.R.; Buckner-Petty, S.A.; Sell-Dottin, K.; D’sOuza, R.S.; Warner, D.O.; Smith, B.B. Methadone Dosing and Postoperative Pain Management in Cardiothoracic Surgery: A Retrospective Cohort Study. Anesthesiology 2024, 141, 1205–1207. [Google Scholar] [CrossRef]
- Salas, W.E.; Cortinez, L.I.; López, R.A.; Rolle, A.; Elgueta, F.; Godoy, C.O.; Giordano, A.; Contreras, V.; Anderson, B.J. Pharmacokinetics of Methadone in Adult Patients Undergoing Cardiac Surgery With Cardiopulmonary Bypass. Anesthesia Analg. 2024, 141, 384–392. [Google Scholar] [CrossRef] [PubMed]
- Singh, K.; Tsang, S.; Zvara, J.; Roach, J.; Walters, S.; McNeil, J.; Jossart, S.; Abdel-Malek, A.; Yount, K.; Mazzeffi, M. Intraoperative Methadone Use Is Associated With Reduced Postoperative Pain and More Rapid Opioid Weaning After Coronary Artery Bypass Grafting. J. Cardiothorac. Vasc. Anesthesia 2024, 38, 1699–1706. [Google Scholar] [CrossRef]
- Weinberg, L.; Johnston, S.; Fletcher, L.; Caragata, R.; Hazard, R.H.; Le, P.; Karp, J.; Carp, B.; Yip, S.W.S.; Walpole, D.; et al. Methadone in combination with magnesium, ketamine, lidocaine, and dexmedetomidine improves postoperative outcomes after coronary artery bypass grafting: an observational multicentre study. J. Cardiothorac. Surg. 2024, 19, 1–16. [Google Scholar] [CrossRef]
- Wong, H.M.K.; Lai, V.K.W.; Chiu, S.L.C.; Wong, W.T.; Wo, S.K.; Zuo, J.Z.; Liu, X.; Wong, R.H.L.; Ho, K.M. Intravenous methadone for pain management in cardiac surgery: a randomised controlled trial with plasma concentration analysis*. Anaesthesia 2025, 81, 51–61. [Google Scholar] [CrossRef]
- Robinson, J.D.; Caruso, T.J.; Wu, M.; Kleiman, Z.I.; Kwiatkowski, D.M. Intraoperative Methadone Is Associated with Decreased Perioperative Opioid Use Without Adverse Events: A Case-Matched Cohort Study. J. Cardiothorac. Vasc. Anesthesia 2020, 34, 335–341. [Google Scholar] [CrossRef]
- Barnett, A.M.; Machovec, K.A.; Ames, W.A.; Homi, H.M.; Turi, J.L.; Koo, J.; Fuller, M.; Jooste, E.H. The effect of intraoperative methadone during pediatric cardiac surgery on postoperative opioid requirements. Pediatr. Anesthesia 2020, 30, 773–779. [Google Scholar] [CrossRef]
- Maxwell, B.G.; Iguidbashian, J.P.; Chang, P.H.; Lines, J. Enhanced recovery and early extubation after pediatric cardiac surgery using single-dose intravenous methadone. Ann. Card. Anaesth. 2020, 23, 70–74. [Google Scholar] [CrossRef] [PubMed]
- Blasiole, B.; Lavage, D.R.; Lin, H.-H.S.; Licata, S.E.; Sivam, S.; Sivam, I.; Le, L.M.; Sadhasivam, S. Intraoperative Methadone Versus Non-Methadone Analgesia in Pediatric Cardiac Surgery: A Retrospective Cohort Study. Children 2025, 12. [Google Scholar] [CrossRef]
- A Lobova, V.; Roll, J.M.; Roll, M.L.C. Intraoperative Methadone Use in Cardiac Surgery: A Systematic Review. Pain Med. 2021, 22, 2827–2834. [Google Scholar] [CrossRef]
- Milam, A.J.; Barnes, J.; Walpole, J. The use of methadone in cardiac surgery: resurgence of an old drug? Curr. Opin. Anaesthesiol. 2025, 39, 52–58. [Google Scholar] [CrossRef] [PubMed]
- Garcia, S.; Mali, M.; Grewal, A. Pro: Methadone Should Be Used as a Part of Enhanced Recovery After Cardiac Surgery Protocol. J. Cardiothorac. Vasc. Anesthesia 2024, 38, 1268–1271. [Google Scholar] [CrossRef] [PubMed]
- Murphy, G.S.; Avram, M.J.; Greenberg, S.B.; Shear, T.D.; Deshur, M.A.; Dickerson, D.; Bilimoria, S.; Benson, J.; Maher, C.E.; Trenk, G.J.; et al. Postoperative Pain and Analgesic Requirements in the First Year after Intraoperative Methadone for Complex Spine and Cardiac Surgery. Anesthesiology 2020, 132, 330–342. [Google Scholar] [CrossRef]
- Laguado, D.; Hu, J.; Watkins, C.; Furstein, J. Intraoperative Utilization of Intravenous Methadone for Postoperative Pain Control. J. PeriAnesthesia Nurs. 2025, 40, 1627–1634. [Google Scholar] [CrossRef]
- Xie, J.; Pan, S.J.; Anderson, T.A.P. A Comprehensive Update on Intraoperative Methadone Use. Anesthesiology 2025, 143, 710–736. [Google Scholar] [CrossRef]
- McClain, M.R.; Subramaniam, K.; Cheema, R.; Lavage, D.R.; Lin, H.-H.S.; Sultan, I.; Sadhasivam, S.; Howard-Quijano, K. Intraoperative Methadone in Adult Cardiac Surgical Patients and Risks for Postoperative QTc Prolongation. J. Cardiothorac. Vasc. Anesthesia 2024, 39, 406–413. [Google Scholar] [CrossRef]
- D’sOuza, R.S.; Esfahani, K.; Dunn, L.K. Pro-Con Debate: Role of Methadone in Enhanced Recovery After Surgery Protocols—Superior Analgesic or Harmful Drug? Anesthesia Analg. 2023, 137, 76–82. [Google Scholar] [CrossRef]
- Eisenbraun, A.; Schroeder, D.; Schaff, H.V.; Martin, E.; Wittwer, E.D. Single-Center Retrospective Comparison of Opioid-Based and Multimodal Analgesic Regimens in Adult Cardiac Surgery. J. Cardiothorac. Vasc. Anesthesia 2023, 37, 1179–1187. [Google Scholar] [CrossRef] [PubMed]
- Bolton, T.M.; Chomicki, S.O.; McKay, W.P.; Pikaluk, D.R.; Betcher, J.G.; Tsang, J.C. Preoperative oral methadone for postoperative pain in patients undergoing cardiac surgery: A randomized double-blind placebo-controlled pilot. Can. J. Pain 2019, 3, 49–57. [Google Scholar] [CrossRef] [PubMed]
- Grant, M.C.; Chappell, D.; Gan, T.J.; Manning, M.W.; Miller, T.E.; Brodt, J.L.; Shaw, A.D.; Engelman, D.; Mythen, M.; Guinn, N.R.; et al. Pain management and opioid stewardship in adult cardiac surgery: Joint consensus report of the PeriOperative Quality Initiative and the Enhanced Recovery After Surgery Cardiac Society. J. Thorac. Cardiovasc. Surg. 2023, 166, 1695–1706.e2. [Google Scholar] [CrossRef] [PubMed]
- Watt, K.M.; Thompson, E.J.; Lam, L.; Zimmerman, K.; Hornik, C.P.; Atz, A.M.; Fernandez, A.; Hupp, S.R.; Bhatt-Mehta, V.; Benjamin, D.K.; et al. Population Pharmacokinetics to Support Intravenous and Enteral Methadone Dosing in Children. J. Clin. Pharmacol. 2025, 66, e70143. [Google Scholar] [CrossRef] [PubMed]
- Sadhasivam, S.; Aruldhas, B.W.; Packiasabapathy, S.; Overholser, B.R.; Zhang, P.; Zang, Y.; Renschler, J.S.; Fitzgerald, R.E.; Quinney, S.K. A Novel Perioperative Multidose Methadone-Based Multimodal Analgesic Strategy in Children Achieved Safe and Low Analgesic Blood Methadone Levels Enabling Opioid-Sparing Sustained Analgesia With Minimal Adverse Effects. Anesthesia Analg. 2021, 133, 327–337. [Google Scholar] [CrossRef]
- Ward, C.T.; Moll, V.; Boorman, D.W.; Ooroth, L.; Groff, R.F.; Gillingham, T.D.; Pyronneau, L.; Prabhakar, A. The impact of a postoperative multimodal analgesia pathway on opioid use and outcomes after cardiothoracic surgery. J. Cardiothorac. Surg. 2022, 17, 1–13. [Google Scholar] [CrossRef]
- Hand, B.A.; Dholakia, R.; Smith, B.B.; Borah, B.J.; Chapital, A.B.; Milam, A.J. Financial Implications of Methadone Use in Cardiothoracic Surgery: A Post Hoc Analysis of a Retrospective Cohort. Anesthesia Analg. 2025, 142, 419–421. [Google Scholar] [CrossRef] [PubMed]
Figure 1.
Methadone pharmacokinetics show both a fast onset and a long-lasting effect. The duration of action is dependent on the administered dose. Reprinted with permission from E. D. Karasch [8].
Figure 1.
Methadone pharmacokinetics show both a fast onset and a long-lasting effect. The duration of action is dependent on the administered dose. Reprinted with permission from E. D. Karasch [8].
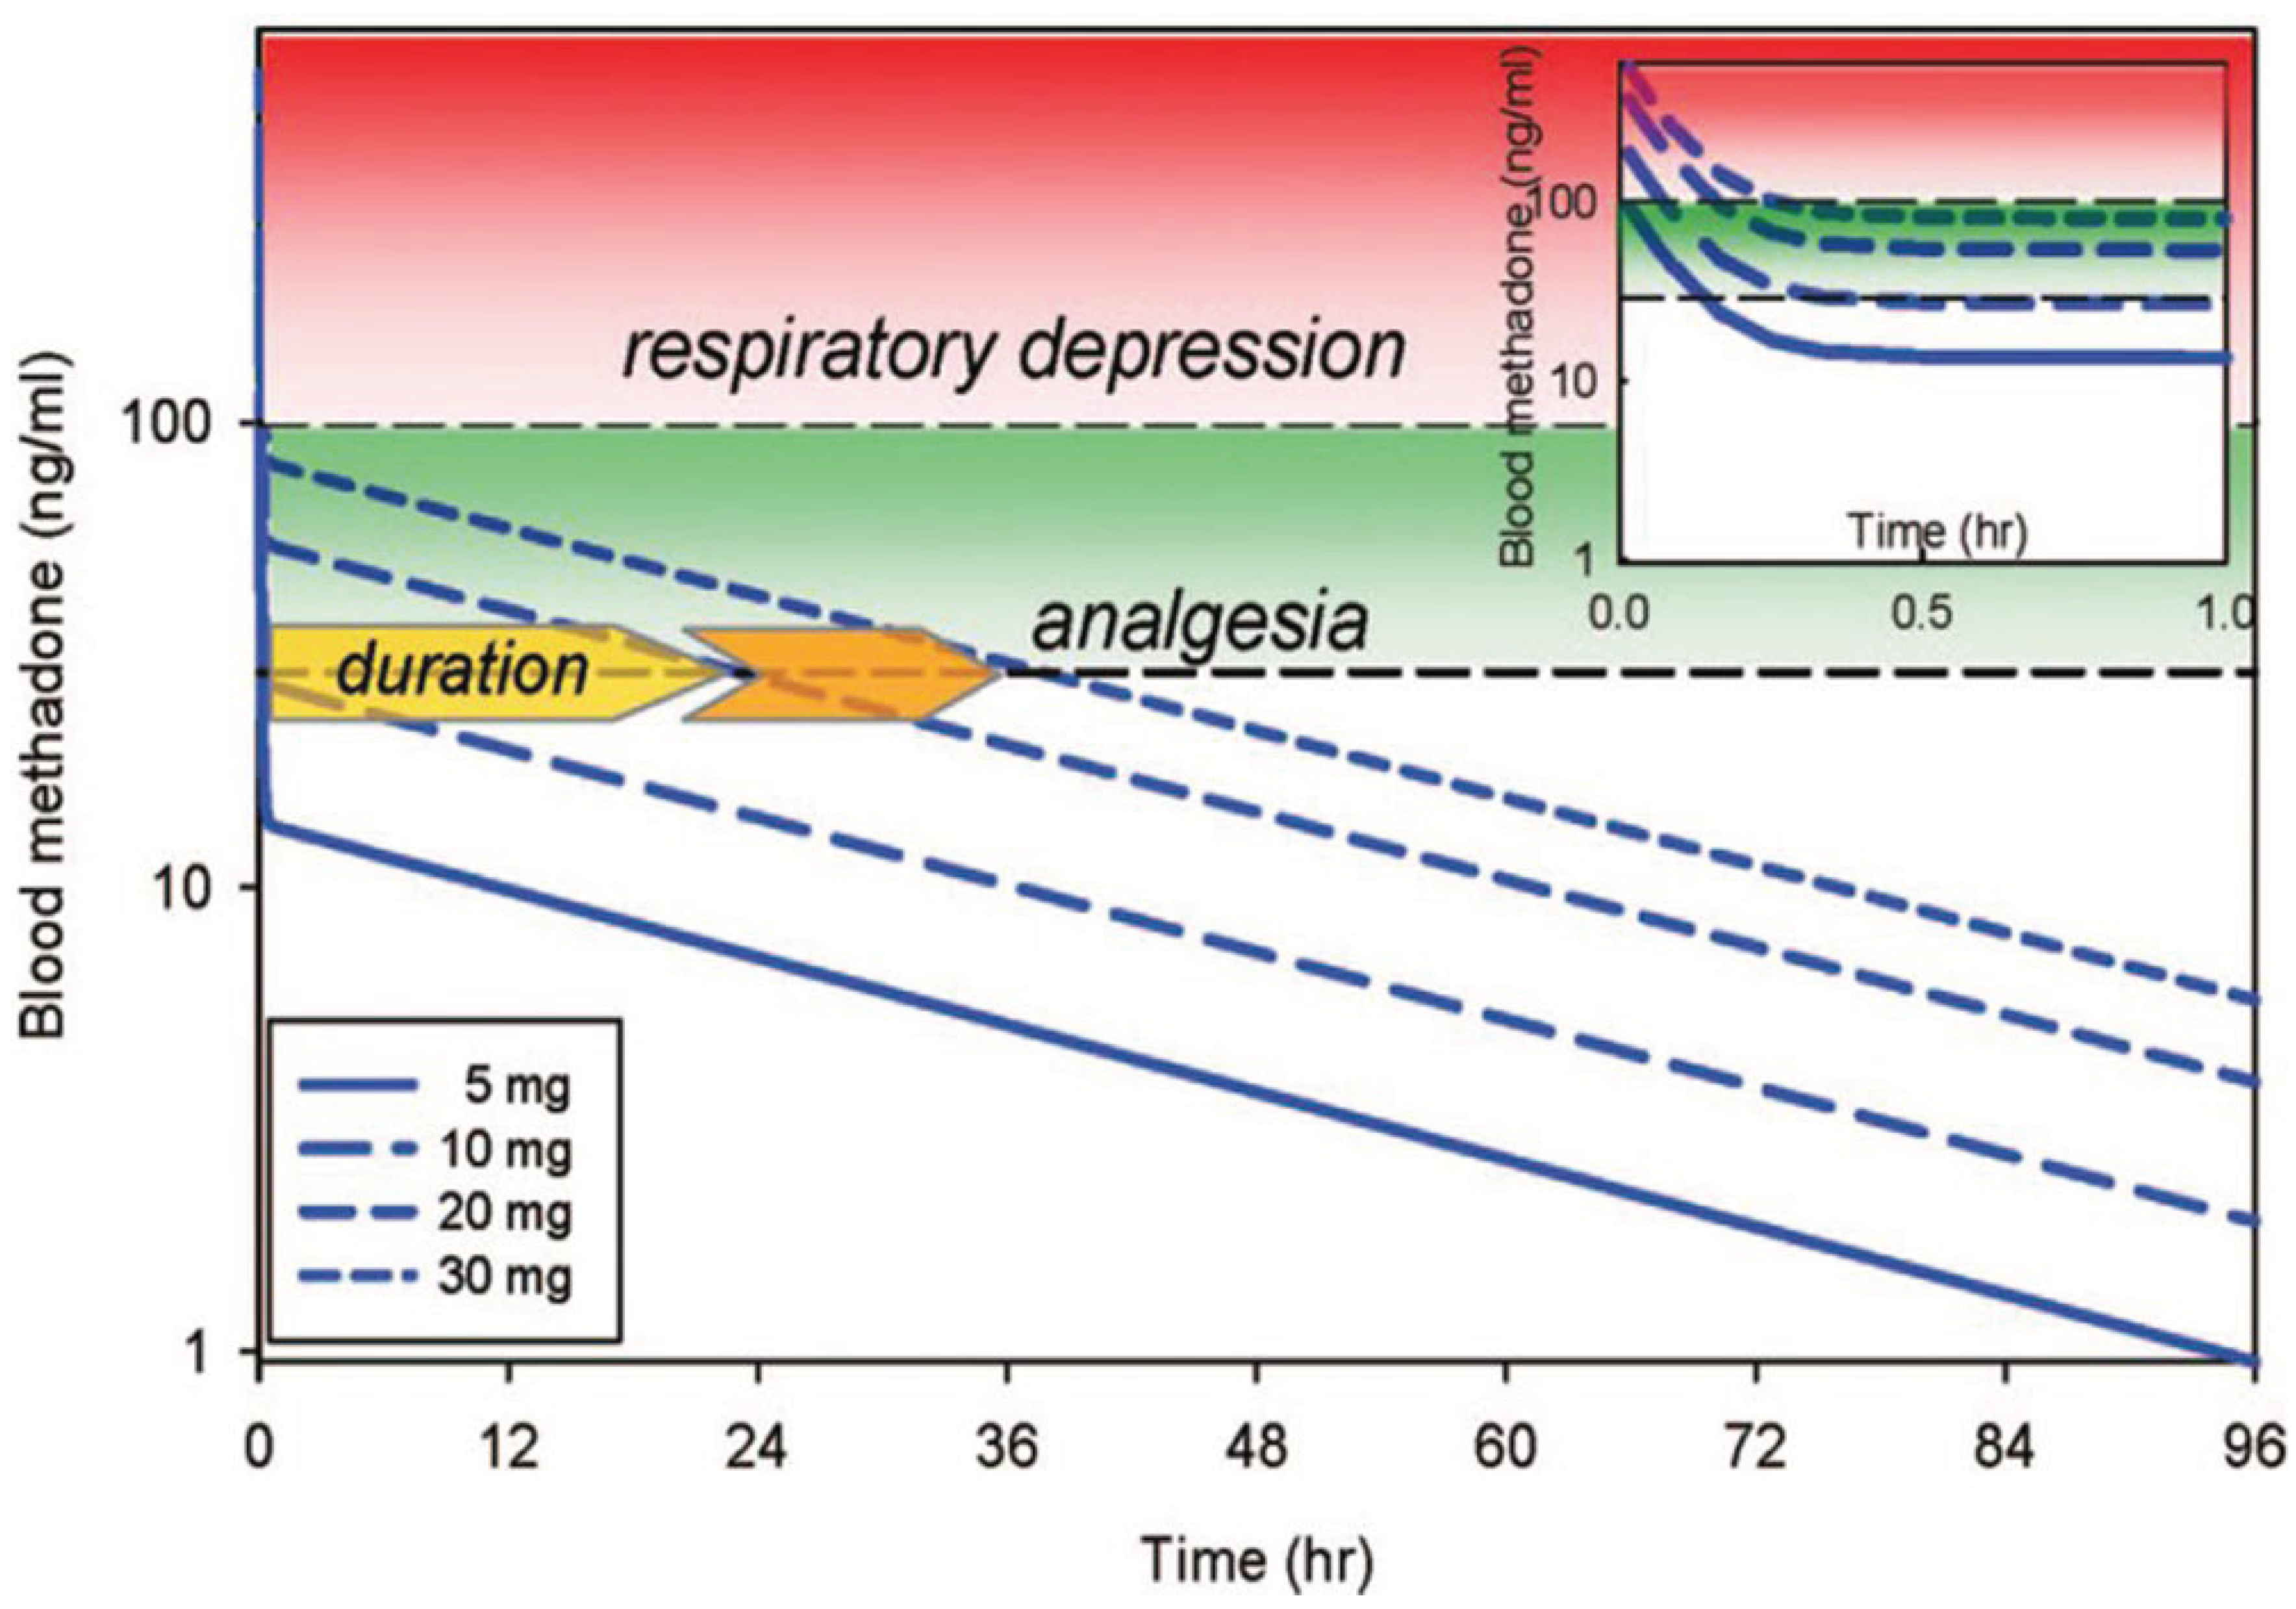
Figure 2.
Search strategy diagram: flow chart of the studies in the narrative review.
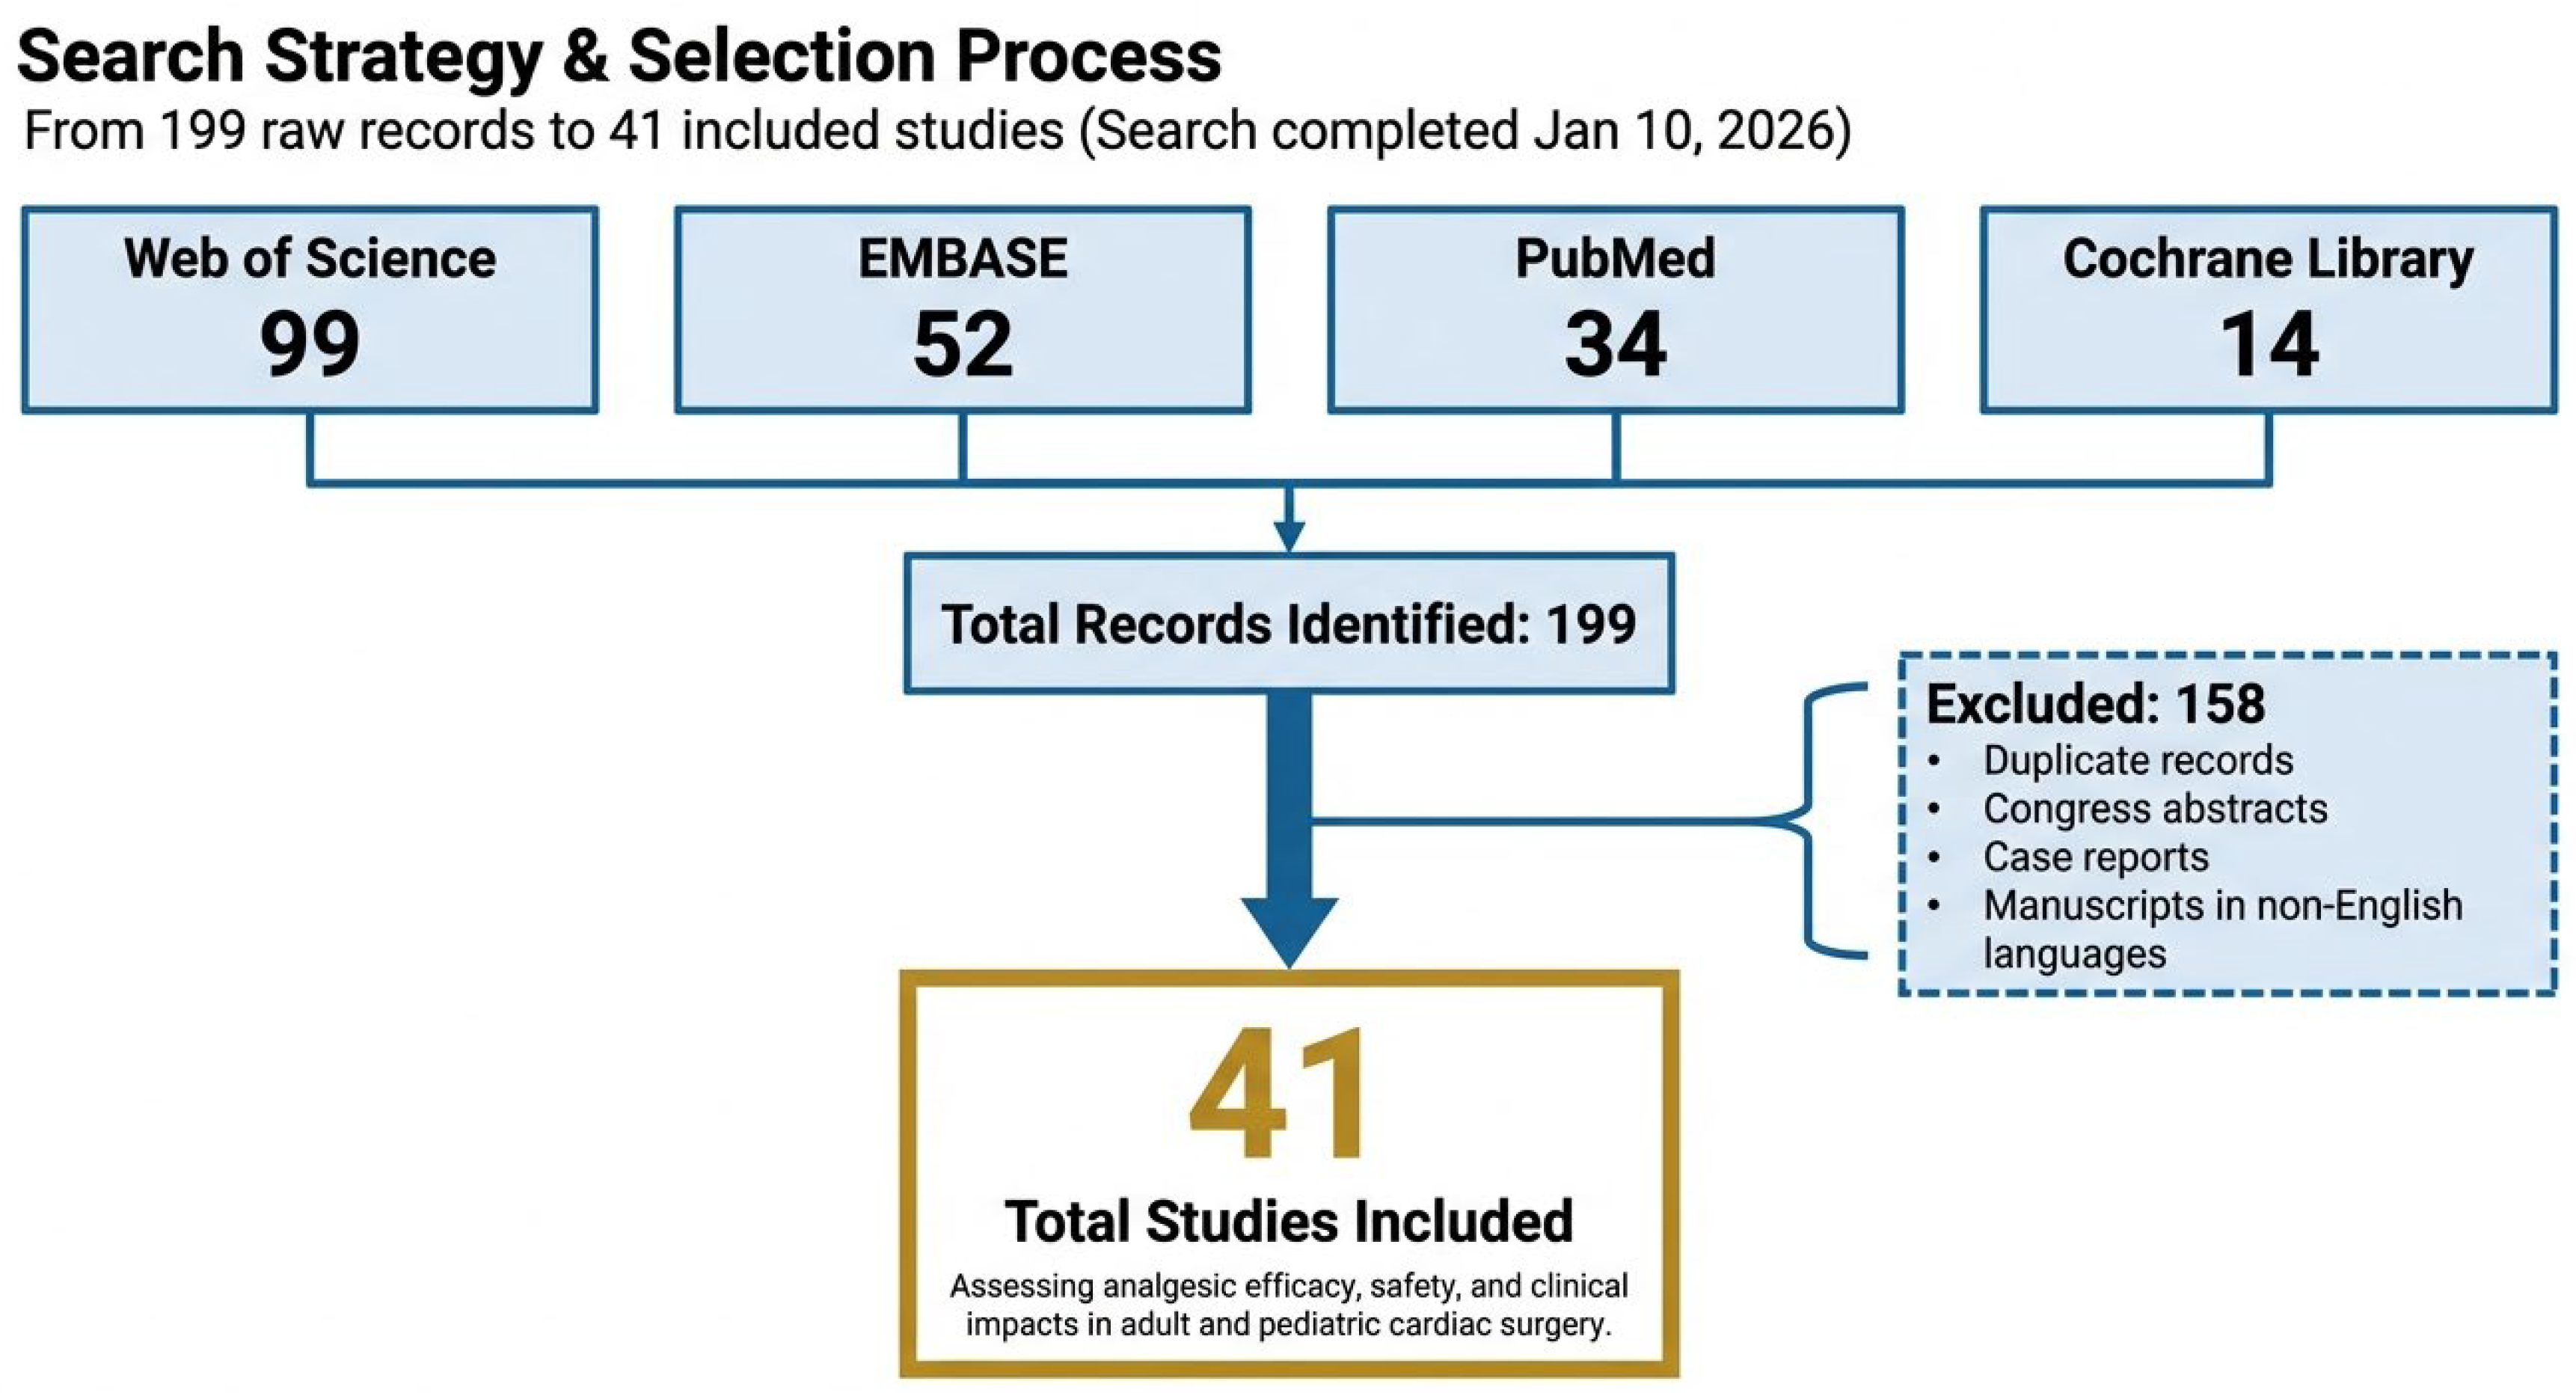
Figure 3.
Methadone plasma concentration decreases significantly after CPB to levels close to or below its therapeutic analgesic range. A proposed strategy to avoid the early offset of its effect is a supplementary bolus of 0.05 mg/kg proposed by [19] after CPB. CPB: cardiopulmonary bypass.
Figure 3.
Methadone plasma concentration decreases significantly after CPB to levels close to or below its therapeutic analgesic range. A proposed strategy to avoid the early offset of its effect is a supplementary bolus of 0.05 mg/kg proposed by [19] after CPB. CPB: cardiopulmonary bypass.
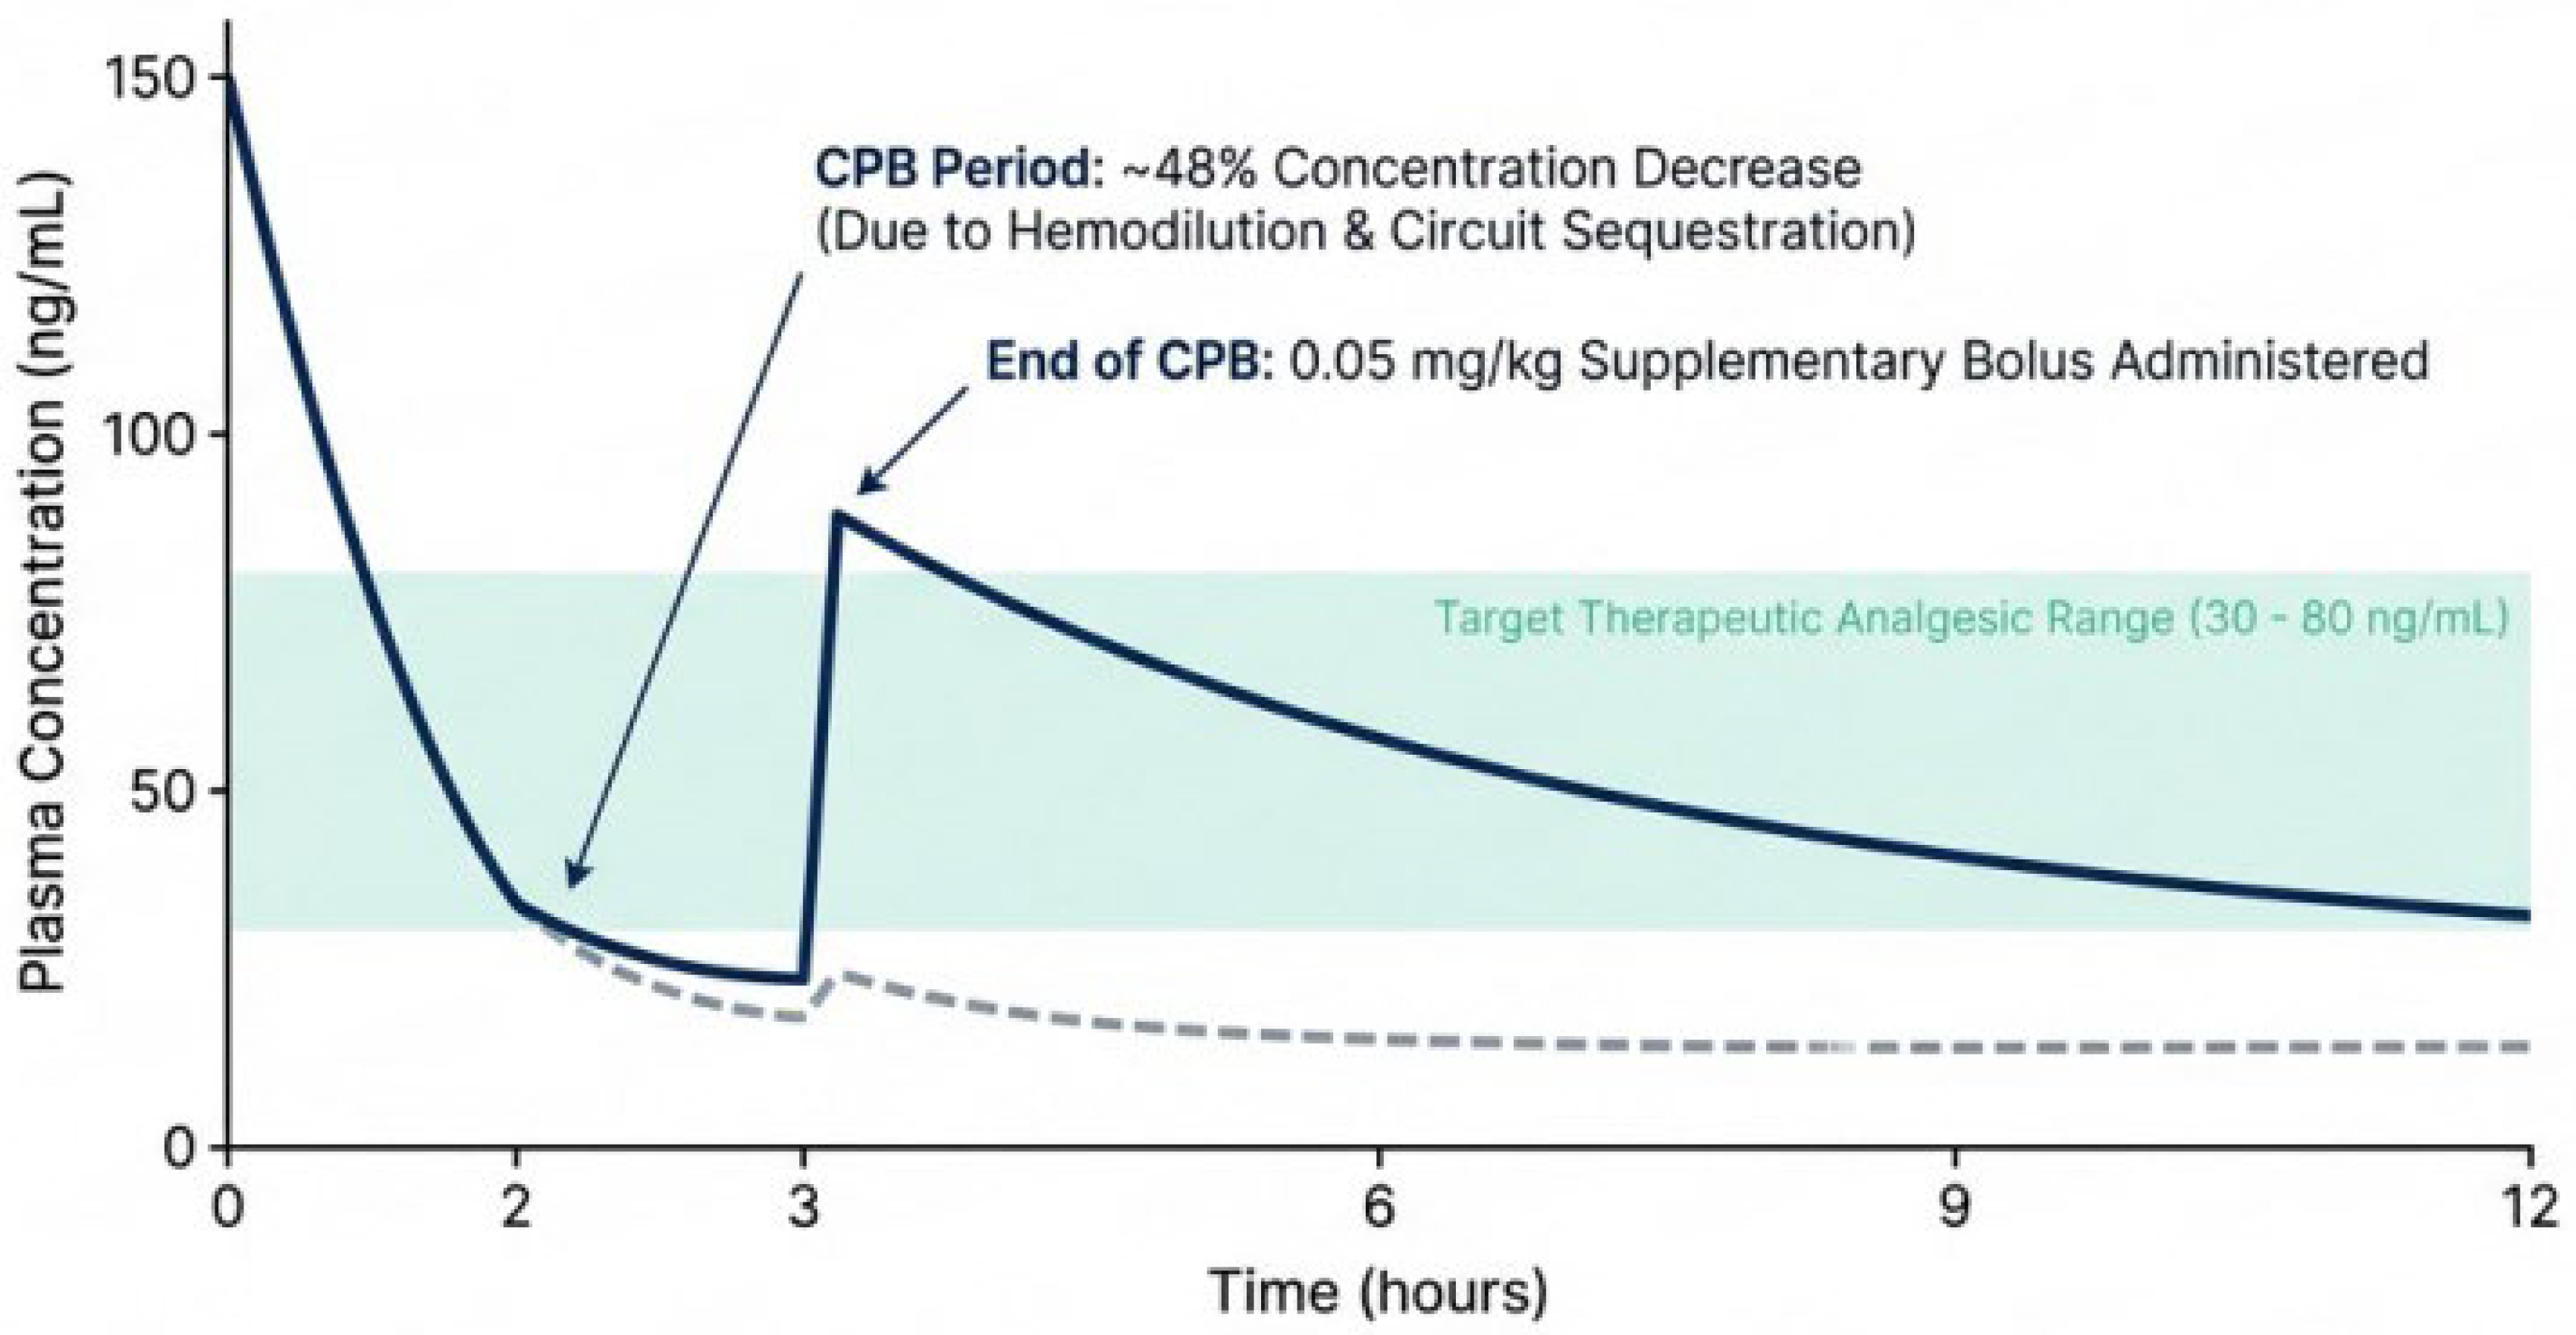

Table 1.
Clinical trials and observational studies on methadone in adult cardiac surgery.
| Author and Year | Study Design | Number of Participants | Groups | Conclusion |
|---|---|---|---|---|
| Udelsmann et al. [10] | Randomized, Double-blind Clinical Trial | 55 | Methadone vs. Morphine vs. Placebo | Methadone might even reduce the incidence of PONV when compared to morphine or placebo. The first analgesic dose in the methadone group was administered later than in the other group. |
| Murphy et al. 2015 [11] | Randomized Controlled, Double-blind Clinical Trial | 156 | Intraoperative Methadone vs. Fentanyl | Methadone resulted in significantly lower pain scores and reduced postoperative morphine requirement. Patients reported improved quality of perceived pain management. No difference in duration of tracheal intubation, hypoxemia, or hypoventilation. The incidence of nausea and vomiting did not differ significantly between groups. |
| Carvalho et al. 2018 [12] | Randomized, Double-blind, Clinical Trial | 104 | Intravenous Methadone vs. Intravenous Morphine | Methadone showed 22% greater efficacy than morphine. It was superior in analgesia, reduced morphine requirement in the first 24h, and improved pain scores at 24h. Patient satisfaction was higher. Differences in the incidence of nausea and vomiting between the methadone and morphine groups were not statistically significant. |
| Burtoft et al. 2020 [13] | Retrospective chart review | 124 | Pre-incisional intravenous methadone (0.15-0.3 mg/kg) vs. No methadone use (other perioperative opioids) | Pre-incisional methadone associated with lower risk of severe pain and less opioid use in the first 24h postoperatively. However, there was no reduction in total cumulative opioid dose or length of hospital stay. This study focused on adults undergoing robotic-assisted mitral valve repair. |
| Wang et al. 2021 [14] | Retrospective Cohort Study | 117 | Intraoperative Methadone vs. Usual Care | Patients in the methadone group showed mild and well-controlled pain relief on postoperative day zero. No significant differences were found in extubation time or use of non-invasive respiratory support. |
| Eisenbraun et al. 2023 | Retrospective, 2-stage study | 4,326 | Opioid-only; Multimodal 1 (preoperative extended-release oxycodone, intraoperative ketamine, postoperative morphine suppository); Multimodal 2 (intraoperative methadone and dexmedetomidine infusion) | Multimodal regimens, particularly Multimodal 2 (methadone + dexmedetomidine), significantly reduced intraoperative and postoperative opioid use, leading to 0 mg OME before hospital discharge and reduced pain scores (especially in the first 0-6 hours for Multimodal 2). |
| Buckner Petty et al. 2024 [15] | Retrospective Cohort Study | 6,856 | Methadone + Ketamine (M+K Group) vs. Methadone Only | The combination prolonged the time to first postoperative opioid and reduced total OMEs consumption on Day 0. No differences in pain scores or other complications beyond POD 0. |
| Edwards et al. 2024 [16] | Retrospective Cohort Study | 11,967 | Methadone vs. No Methadone | Patients in the methadone group had lower mean pain scores up to postoperative day 7. Lower total opioid consumption from POD0 to POD6. No increased incidence of PONV was found. The incidence of postoperative complications did not differ between groups. |
| La Colla et al. 2024 [17] | Retrospective Cohort Study | 289 | Intravenous Methadone vs. Intrathecal Morphine in ERACS protocol | Intrathecal morphine associated with lower pain scores on POD 0, but no difference in opioid consumption or outcomes beyond POD 0. Methadone can be considered a safe and effective alternative. |
| Milam et al. 2024 [18] | Retrospective Cohort Study | 12,017 | Different Methadone dosages vs. No Methadone | Higher methadone doses associated with more significant reductions in pain and opioid consumption. All dosages significantly prolonged the time to first postoperative opioid requirement. Higher methadone doses were associated with a significantly increased risk of developing delirium. |
| Salas et al. 2024 [19] | Pharmacokinetic Study | 29 | Methadone in patients undergoing CPB | Plasma methadone concentrations dropped 48% during CPB due to hemodilution and sequestration. Plasma concentrations at the end of surgery would be below the range for effective analgesia. A supplemental dose of 0.05 mg/kg after CPB may compensate for the decrease. |
| Singh et al. 2024 [20] | Observational Study | 1,338 | Intraoperative Methadone vs. No Methadone | Associated with a slightly longer duration of initial mechanical ventilation, but clinical significance is questionable as most were extubated within 24 hours. Reduced postoperative pain and accelerated opioid weaning. Considered safe. |
| Weinberg et al. 2024 [21] | Multicenter Observational Study | 263 | Multimodal protocol (methadone + magnesium, ketamine, lidocaine, dexmedetomidine) vs. Usual care | Reduced mechanical ventilation time, postoperative pain scores, and opioid consumption without increased adverse events. |
| Wong et al. 2025 [22] | Randomized Controlled Clinical Trial | 86 | Intravenous Methadone vs. Intravenous Morphine | Methadone provides superior analgesic control, resulting in significantly lower pain scores. A 63% reduction in postoperative morphine requirement at 24 h and 69% at 72 h. Methadone concentrations, despite falling during CPB, remained above the minimum effective analgesic concentration for approximately 24 h after administration. No differences were observed in opioid-related adverse effects within 72 hours of surgery, including nausea and vomiting. |
CPB: cardiopulmonary bypass; OME: oral morphine equivalents; POD: postoperative day.
Table 2.
Observational studies in pediatric patients undergoing cardiac surgery.
| Author and Year | Study Design | Number of Participants | Groups | Conclusion |
|---|---|---|---|---|
| Robinson et al. 2019 [23] | Retrospective Cohort Study with case matching | 74 | Intraoperative Methadone vs. Controls | The methadone group required less intraoperative opioids, in the first 12 hours postoperative, and during the first 36 hours postoperative. There was no association with extubation time, ICU length of stay, pain scores, or adverse events such as extubation failure, QTc prolongation, or in-hospital mortality. |
| Barnett et al. 2020 [24] | “Before and After” Study | 198 | Pre-intervention group vs. Post-intervention group | There was a significant decrease in intraoperative opioid and sedative doses in both age groups. In non-neonates, there was also a reduced need for opioids in the first 24h postoperative. |
| Iguidbashian et al. 2020 [25] | Retrospective Case Series | 24 | Multimodal analgesic regimen centered on intravenous methadone | High rate of extubation in the operating room; mean time to first supplementary opioid dose of 5.1 hours; modest supplementary opioid consumption; no reintubations required. |
| Blasiole et al. 2025 [26] | Retrospective Cohort Study | 287 | Intraoperative Methadone vs. Non-methadone Analgesia | There were no significant differences in postoperative opioid use, mean/maximum pain, antiemetic use, reintubation, or naloxone use in adjusted analyses. Hospital length of stay was 2.62 times longer in the methadone group for children ≤6 years. |
ICU: intensive care unit.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.