
Submitted:
07 January 2026
Posted:
08 January 2026
You are already at the latest version
Abstract
Background: Multimorbidity, the presence of two or more chronic health conditions in an individual, presents a significant challenge for healthcare systems worldwide. Physical activity (PA) is an important intervention for the management of chronic health conditions and prevention of disease complications. However, individuals with multimorbidity face unique barriers to PA participation. Artificial intelligence (AI) has emerged as a promising tool to enhance digital health interventions, offering tailored PA promotion. This review synthesised the current evidence on trials using AI-integrated digital intervention tools (including machine learning, natural language processing and predictive analysis) designed to support PA among individuals with multimorbidity.Methods: A rapid review was conducted following PRISMA guidelines. A comprehensive search was performed across six electronic databases (MEDLINE, EMBASE, CINAHL, OVID, Cochrane Library, PsycINFO, Scopus) covering studies from January 2015 to May 2025. Eligible studies were randomised controlled trials (RCTs) involving adults (≥18 years) with multimorbidity using AI-informed digital health interventions to promote PA. Two reviewers independently screened the articles and extracted the data. Owing to the heterogeneity of the included studies, meta-analysis was not possible, and the results were narratively synthesised.Results: Our initial search identified 276 studies. After removing duplicates and screening titles, abstracts, and full texts, 4 studies met the inclusion criteria. All included studies were RCTs that used AI-integrated digital interventions to promote PA in adults with multimorbidity. AI technology interventions included personalised mobile applications (n=2), decision-support systems (n=1), and socially assistive robotics (n=1). The study populations ranged from generically described multimorbid individuals to those with specific cardiometabolic and respiratory combinations of multimorbidity. PA outcomes were assessed through both self-report questionnaires and objective fitness measures. Attrition was common, particularly in longer-duration studies. While some improvements in PA have been reported, overall evidence remains limited and heterogeneous.Conclusions: The limited number of RCTs suggests emerging but inconclusive evidence on the effectiveness of AI-integrated digital health interventions to support PA in multimorbid individuals. Interventions may offer benefits, but heterogeneity in study design, population, and outcomes limits generalisability. Further research using consistent data collection and outcome measures, as well as longer-term follow-up, is needed.
Keywords:
multimorbidity
; physical activity
; artificial intelligence
; machine learning
; digital health
; mobile applications
; wearable devices
; telehealth
; exercise
; chronic conditions
Background
Multimorbidity, the coexistence of two or more chronic health conditions in an individual, affects over 25% of adults in high-income countries and presents significant healthcare challenges [1,2]. Physical activity (PA) has been shown to offer benefits across multiple conditions simultaneously, improving cardiovascular health, mental health, and overall quality of life [3]. However, multiple barriers, including physical limitations, the inaccessibility of specialist exercise support, and competing health management priorities, impede regular PA engagement among people with multimorbidity [4,5]. Earlier evidence shows that despite the known benefits, individuals with multimorbidity demonstrate lower adherence to PA guidelines than those with single conditions do, highlighting the need for innovative and integrated approaches to support this population [5]. Artificial intelligence (AI) approaches offer promising capabilities to enhance PA interventions through more accessible, personalised support.
Recent developments in machine learning algorithms, predictive analytics, and natural language processing have enabled tailored delivery of PA recommendations specific to an individual’s combination of conditions, preferences, and exercise capabilities [6,7,8,9]. AI-integrated applications can analyse patterns in user behaviour, adapt to changes in health status, and provide real-time feedback in ways that traditional interventions cannot [6]. Despite these promising applications, research specifically examining AI tools for PA promotion in multimorbidity remains limited. Sumner et al. (2023) [8] reviewed AI applications in physical rehabilitation and reported that while AI-supported systems have potential for personalising exercise regimens, the clinical effects are inconsistent, and implementation barriers include technology literacy and user fatigue. Chaparala et al. (2025) [9] identified promising AI applications for analysing health data in multimorbidity but noted a distinct absence of longitudinal studies evaluating AI’s impact on PA engagement in this population. Zangger et al. (2023) [3] systematically reviewed digital health interventions for PA in people with chronic conditions, documenting small effects and explicitly noting the knowledge gap regarding interventions addressing multiple concurrent conditions. Moreover, Bricca et al. [10] discovered that exercise therapy reduced physical and psychosocial symptoms related to multimorbidity. Edwards et al. (2024) [11] conducted a comprehensive overview of systematic reviews covering exercise interventions across 45 different long-term conditions, specifically identifying the intersection of multimorbidity and technology-enhanced interventions as a critical evidence gap. Despite the growing body of research on both AI applications for health and PA interventions for chronic conditions, to our knowledge, there has been no systematic synthesis of evidence examining the role of AI tools in promoting PA among people managing multiple conditions simultaneously (multimorbidity). This rapid review aims to systematically collate and synthesise the existing evidence from trials using AI-informed digital tools designed to promote PA in people with multimorbidity.
Methods
Study Design
This rapid review followed the PRISMA extension for Scoping Reviews (PRISMA-ScR) [12] and adapted systematic review methods to accelerate the evidence synthesis process. Rapid reviews are well suited to emerging topics where timely synthesis is needed to inform evolving technologies.
Eligibility Criteria
Inclusion criteria:
- Randomised controlled trials
- Adults (≥18 years) with multimorbidity (≥2 chronic conditions)
- Digital interventions incorporating AI (e.g., ML, NLP, predictive analytics)
- Interventions aimed at promoting PA
- English-language publications from Jan 2015--May 2025
- Full-text availability
Exclusion criteria:
- Studies focused on a single condition
- Nondigital interventions
- Studies without true AI integration
- No PA outcomes
- Non-RCT designs
- Studies involving only children/adolescents
- Editorials, protocols, and opinion pieces
Search strategy: The search strategy was developed in consultation with an information specialist with expertise in systematic reviews. We used a combination of Medical Subject Headings (MeSH) terms and free-text keywords related to three main concepts: (1) multimorbidity, (2) physical activity, and (3) AI-informed digital health interventions.
The key search terms included the following:
- For multimorbidity: “multimorbidity”, “comorbidity”, “multiple chronic conditions”, “multiple long-term conditions”, “chronic disease”
- For physical activity: “physical activity”, “exercise”, “fitness”, “movement”, “physical fitness”, “cardiovascular training”, “walking”, “resistance training”, “aerobic exercise”, “exercise support”, “strength training”, and “exercise therapy”.
- AI-informed digital health interventions include “artificial intelligence”, “machine learning”, “deep learning”, “natural language processing”, “predictive analytics”, “digital health”, “mHealth”, “eHealth”, “telehealth”, “mobile application”, “smartphone”, “wearable”, and “digital intervention”.
The search strategy was piloted in MEDLINE and refined before being adapted for other databases. A draft search strategy for MEDLINE is provided in Appendix A. The MEDLINE search strategy was developed with an information specialist and adapted for each database.
Study Selection
Two independent reviewers screened titles and abstracts (AD and CP) via Rayyan QCRI, a web-based systematic review software designed to facilitate collaboration and streamline the screening process. The full texts of potentially eligible studies were retrieved. Discrepancies were resolved through discussion. A PRISMA flow diagram was used to document the selection process [12].
Data Extraction and Quality Assessment
A standardised extraction form was piloted and used to collect data on study characteristics, population details, intervention components, AI tools, PA outcomes, and engagement.
Owing to the small number of studies and their heterogeneity in design, intervention types, and outcome measures, a meta-analysis was not feasible. A narrative synthesis was conducted to summarise the findings.
Results
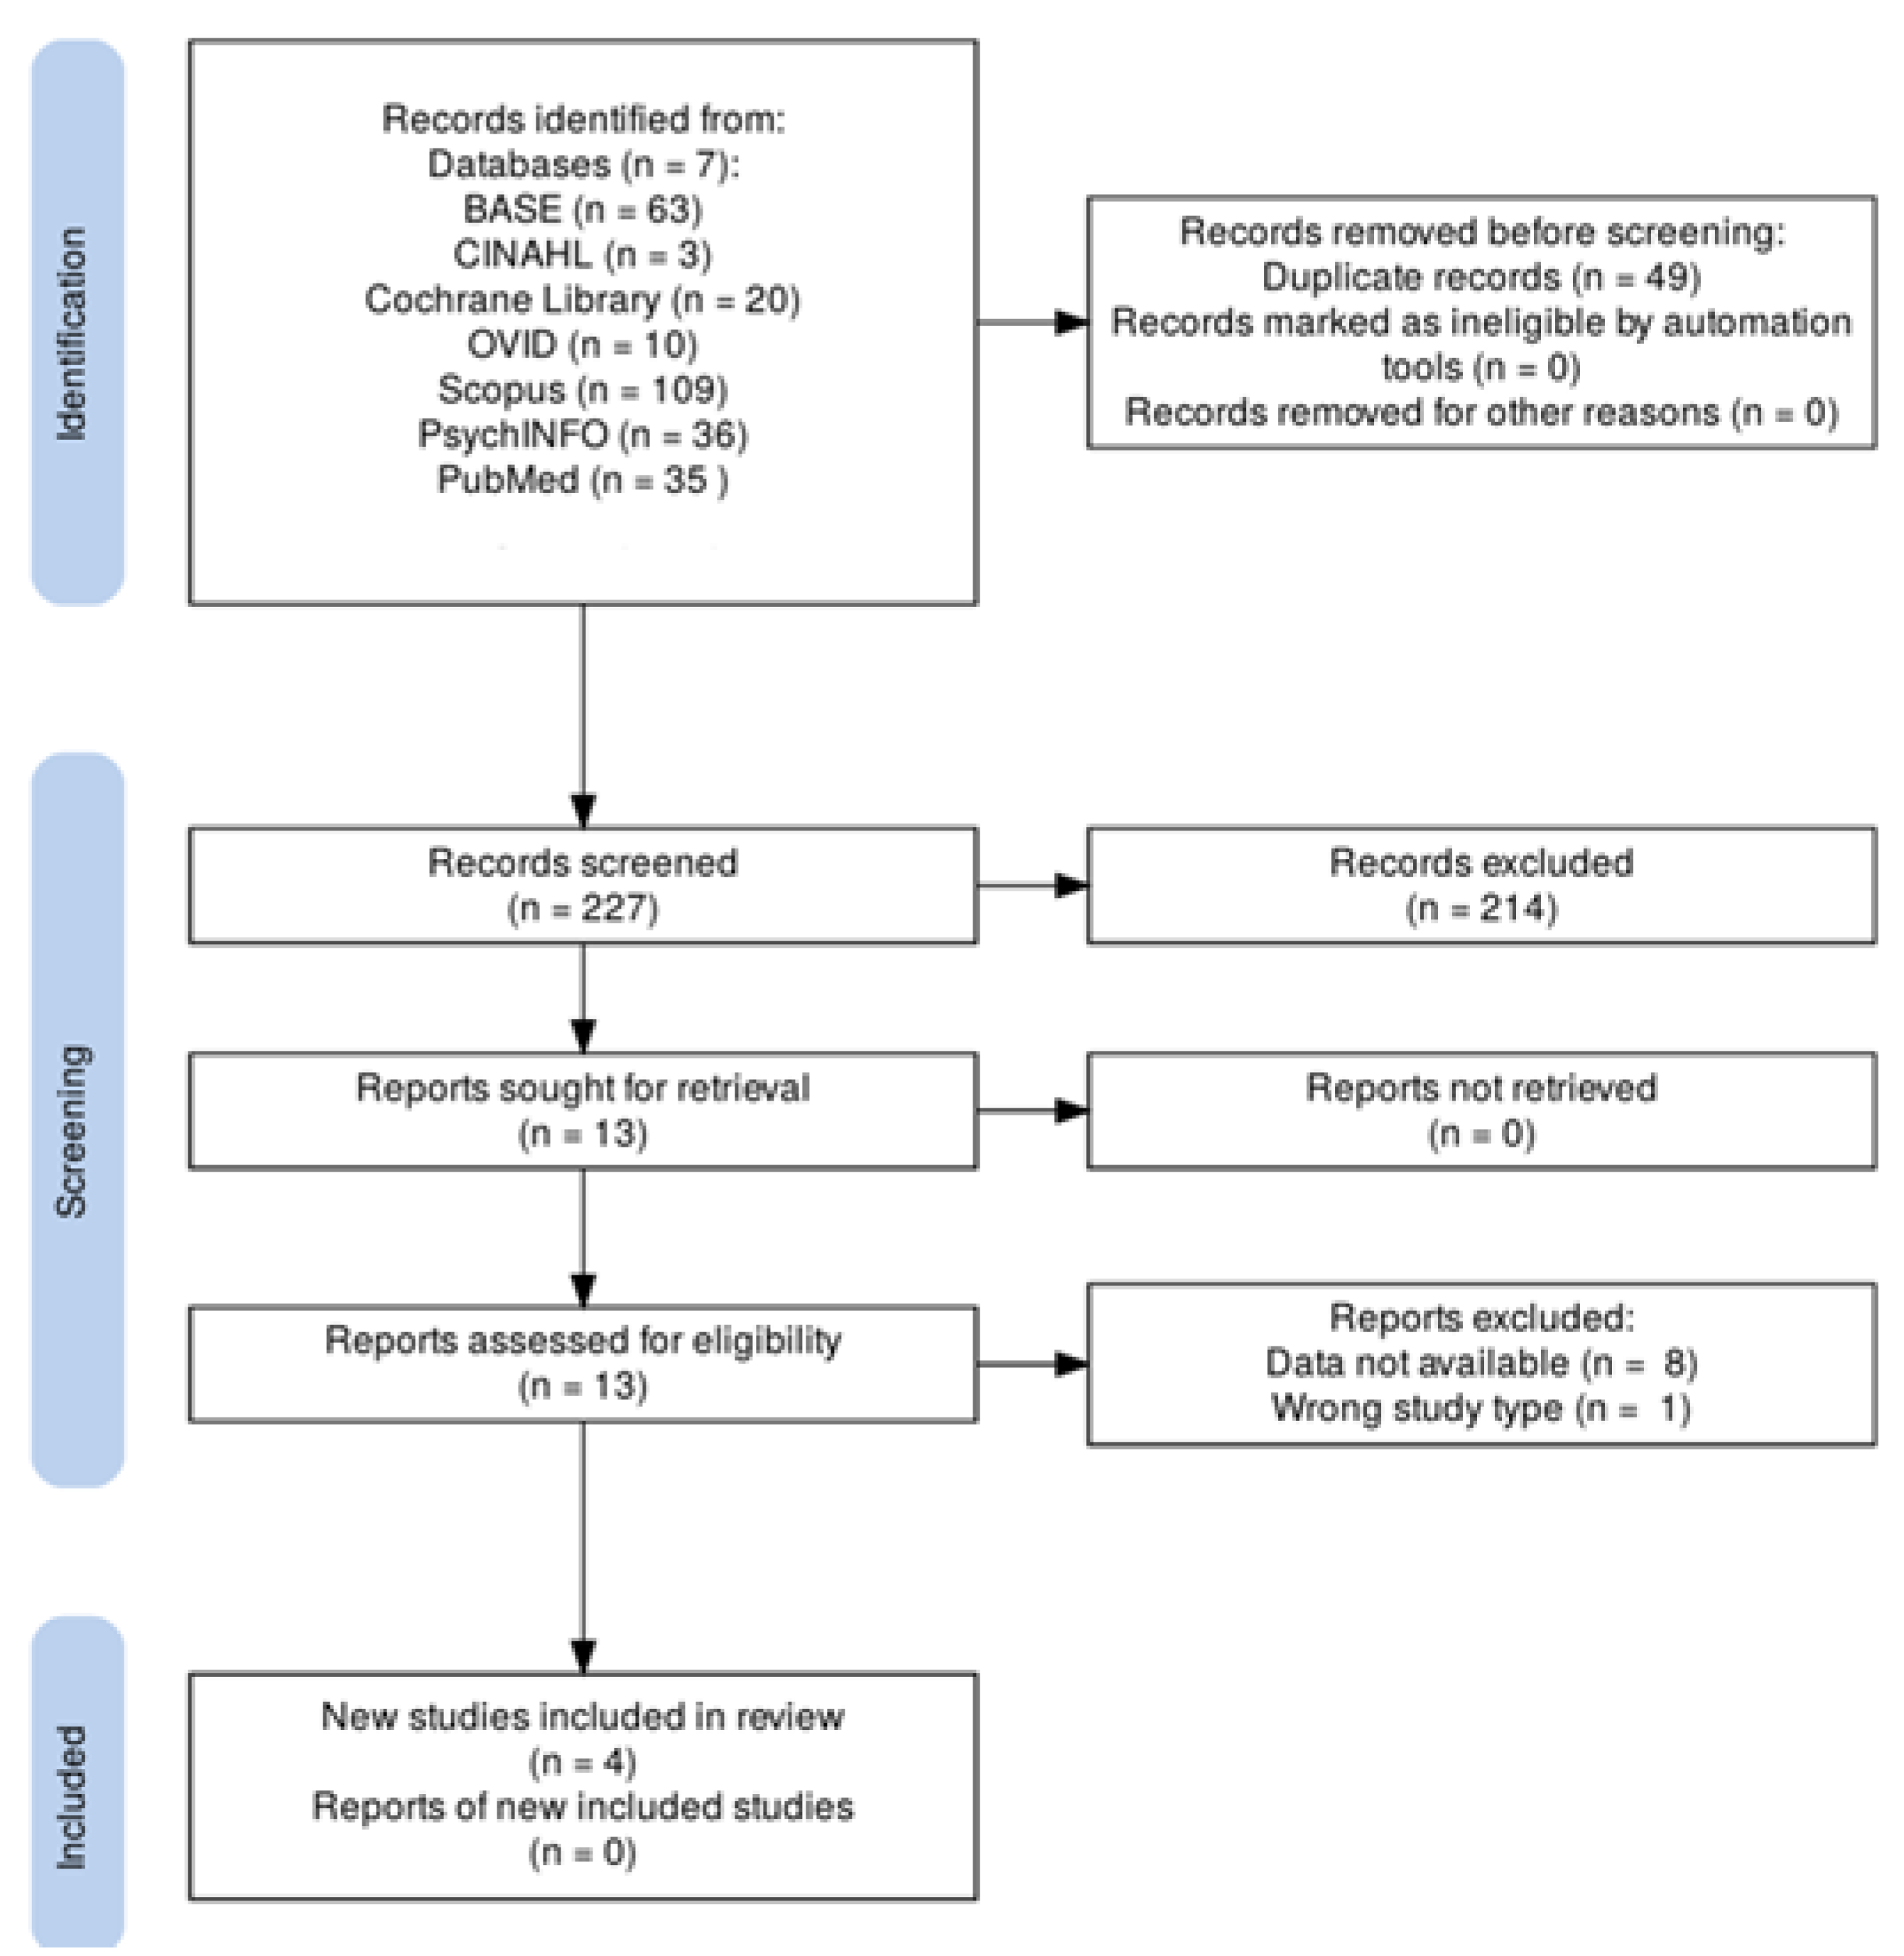
Our search identified 276 studies. After 49 duplicates were removed, 227 records were screened by title and abstract. Thirteen studies were assessed in full, eight of which were excluded because of ongoing trial status without available results, and one was excluded because it was not an RCT. Ultimately, four studies met the inclusion criteria for this review. The flow of studies included in the review is shown in a PRISMA diagram (Figure 1).
Study Characteristics
The four included studies were conducted in Spain, China, Denmark, and New Zealand between 2018 and 2024 [13,14,15,16]. The sample sizes ranged from 8 to 460 participants. All studies were RCTs evaluating the impact of AI-enhanced digital interventions to promote PA in adults with multimorbidity. Study populations varied: two focused on condition-specific cohorts (e.g., cardiopulmonary disease) [13,14], whereas others included broader or undefined multimorbid populations [15,16]. The age ranges were typically mid-to-late adulthood, and most samples were balanced in terms of sex, although demographic breakdowns were variably reported. These are summarised in the data extraction table included in Appendix B.
Digital Interventions
Intervention modalities included mobile health applications (n=2), AI-driven exercise prescriptions (n=1), and socially assistive robotics (n=1). Carrasco-Hernandez et al. [16]. involved an AI-enhanced app to support smoking cessation while monitoring PA. In comparison, Liu and Zhang [15] used an AI algorithm to generate personalised exercise regimens that combine aerobic and resistance training. The SELFBACK app provided self-management support for back pain in a study by Øverås et al. [13], and a robotic system was used in a pilot RCT by Broadbent et al. [14] that targeted older adults with COPD to support medication adherence and exercise engagement. The intervention duration ranged from 12 weeks to 12 months.
AI Tools
AI was used to personalise and adapt interventions in all studies. Techniques included machine learning algorithms for tailoring exercise prescriptions, recommender systems to deliver motivational content, natural language processing for decision support, and robotic automation with real-time feedback mechanisms. In some cases, AI components are adapted based on user interaction or clinical data inputs, allowing for progressive personalisation throughout the intervention.
Outcomes
PA outcomes were assessed via both self-reported measures (e.g., IPAQ, questionnaires) and objective metrics (e.g., 6-minute walk test, cardiopulmonary assessments, muscle strength tests). Broadbent et al. [14] reported statistically significant improvements in PA frequency in patients undergoing rehabilitation following hospital discharge (mean difference −4.53, 95% CI −7.16--−1.92). Other reported outcomes included an insignificant reduction in hospital admission (p>0.99), no change in functional status (p=0.11) and improved medication adherence postintervention (p=0.03)[14]. Øverås et al. [13] reported that the effect of the SELFBACK app was not significantly modified by multimorbidity or additional MSK pain and that the app’s benefit was consistent across both subgroups (p interaction at 9 months = 0.84). In Liu and Zhang’s [15] review, self-reported PA was a secondary outcome, with participants noting a general decrease in functional difficulty following the use of AI-generated exercise prescriptions (p<0.01). The primary focus of the study was to compare different AI-prescribed exercise routines, with the main outcomes being BMI changes and metrics of cardiopulmonary function (e.g., NT-proBNP postintervention ~239.6 pg/mL, p <0.05)[15].
Follow-Up Period and Attrition
The follow-up duration varied from 12 weeks to 12 months. The longest study (12 months) had the highest attrition, with 58% of the intervention group and 63% of the control group losing adverse effects; however, this study did not explicitly state what was included [16]. Shorter studies (12 weeks) resulted in better retention [15]. Attrition was inconsistently reported across studies, but where described, dropout appeared more pronounced in longer interventions, potentially limiting the interpretation of long-term effects. Moreover, attrition rates may have artificially inflated the ability of the AI app to promote PA, since participants who dropped out were not included in the post-result analysis [15].
Discussion
Main Findings
In this study, we aimed to systematically review randomised controlled trials evaluating the use of AI-integrated digital interventions to promote PA in adults with multimorbidity. We found four eligible RCTs that demonstrated the feasibility of embedding AI technologies into digital health tools targeted at this population. Despite variation in study aims, intervention types, and populations, all trials utilised AI to personalise or adapt PA-related content and reported some improvements in PA behaviours, functional outcomes, or engagement metrics [13,14,15,16]. However, PA was not consistently the primary outcome in all the studies, and the effect sizes were modest. Objective PA improvements were observed in two studies, whereas others reported secondary benefits or engagement without statistically significant limitations in follow-up duration and high attrition, particularly in longer trials, which may suggest poor long-term adherence and sustained impact. Overall, while AI-informed digital interventions show early promise for supporting PA in people with multimorbidity, the current evidence base is limited by small sample sizes, inconsistent outcome reporting, and methodological variability [13,14,15,16].
Comparison with the Literature
The literature on the integration of AI to promote PA is limited, with many reviews focusing on digital health interventions to promote PA without AI integration [3]. Most of these interventions rely on static, one-size-fits-all approaches that do not adapt to the complex and evolving needs of individuals with multiple chronic conditions. Our rapid review aims to position AI-integrated technologies at the forefront of promoting PA, highlighting their potential to deliver personalised, adaptive support that could better address the challenges faced by people with multimorbidity. A systematic review and meta-analysis by Zangger et al. [3] revealed that digital health interventions had only a minimal effect on PA in patients with multiple chronic conditions. However, this rapid review revealed that AI-embedded health systems, which use algorithms to tailor content and respond dynamically to user input, demonstrated greater potential to benefit patients with multimorbidity. These systems may help overcome traditional barriers to PA by offering more responsive and context-sensitive support. Previous reviews have also investigated digital interventions for patients with a single chronic condition. For example, a review by Letton et al. [17] focused on the promotion of PA in patients with chronic kidney disease only, reflecting a common trend in the literature toward condition-specific approaches. While these studies provide valuable insights, they do not capture the unique complexities and care needs associated with managing multiple conditions simultaneously. Our review is therefore unique in that it investigates AI integration specifically within multimorbid patient populations. This focus addresses a key gap in current research and contributes to the growing recognition of the need for more inclusive, personalised, and scalable digital health solutions for individuals managing multimorbidity.
Strengths and Limitations
To our knowledge, this review is the first to focus specifically on AI-integrated digital interventions for promoting PA in populations with multimorbidity. A key strength of this review lies in its comprehensive and systematic search strategy, which was developed in consultation with an information specialist and designed to capture a wide range of relevant studies across major databases. Additionally, the use of structured data extraction ensured consistency in how information was gathered and synthesised across studies, contributing to the reliability of the findings. Another notable strength is the specific focus on multimorbidity—an area often overlooked in digital health and PA research. By including only trials with adults managing two or more chronic conditions, this review addresses an important gap in the current literature and aligns with broader calls for more inclusive and person-centred health interventions. However, there are several limitations to consider. By restricting inclusion to RCTs, we may have excluded valuable insights from other study designs, such as feasibility studies, pilot programs, or real-world implementation research, which are especially relevant in emerging fields such as AI in healthcare. While lower on the evidence hierarchy, observational studies could have offered additional perspectives on user engagement, acceptability, and longer-term use of AI technologies. Furthermore, an evidence base is still lacking. Many studies investigating AI interventions for PA in multimorbid populations are ongoing, and we identified eight RCT protocols without published results. This limits the current ability to assess the full scope and effectiveness of such interventions. As a result, our synthesis likely represents an early-stage overview, with the potential for significant new insights to emerge as additional trials are completed and published. Another limitation is that although the included studies involved participants with multimorbidity, several did not focus primarily on PA as the main outcome. For example, one study primarily targeted smoking cessation, with PA measured as a secondary endpoint [16]. In such cases, PA outcomes may have been underpowered or not sufficiently reported, limiting the accuracy with which the specific impact of AI on PA behaviour can be assessed. Finally, the heterogeneity of interventions and outcome measures made it difficult to draw generalizable conclusions or conduct a quantitative synthesis. Had broader study designs or interim findings been included, a more nuanced and comprehensive understanding of the effectiveness, feasibility, and implementation of AI-driven PA interventions in this complex population might have been achieved.
Conclusions
There is emerging but limited evidence that AI-enhanced digital interventions may support PA in adults with multimorbidity. While technologies such as tailored exercise algorithms, mobile apps, and robotics demonstrate potential, current trials are small, heterogeneous, and often not powered to detect clinically meaningful changes in PAs. Future studies should prioritise clearly defined multimorbid populations, standardised PA outcome measures, improved follow-up measures, and more consistent reporting of AI features and user engagement.
Disclaimer
The views expressed in this publication are those of the author(s) and not necessarily those of the NHS, the National Institute for Health Research or the Department of Health and Social Care.
Ethics approval and consent to participate: Not applicable.
Consent for publication: Not applicable.
Availability of data and materials: Not applicable.
Authors’ Contributions: HDM conceived the study, AD, CP and JK carried out data extraction and wrote the first draft of the paper. All authors contributed towards data interpretation and critically editing the manuscript.
Funding Statement: HDM has received funding from the National Institute for Health and Care Research ‘Multiple Long-Term Conditions (MLTC) Cross NIHR Collaboration (CNC)’ (NIHR207000).
Acknowledgments
Not applicable.
List of Abbreviations
AI: Artificial Intelligence
PA: Physical Activity
RCT: Randomised Controlled Trial
MLTC: Multiple Long Term Conditions
CNC: Cross NIHR Collaboration
Appendix A. Table with Full Search Strategy Including Databases Searched, Search Terms Used, and Number of Results Retrieved
| Database | Terms Used | Results (English) |
| BASE | (physical activity/or exercise/or exercise therapy/or physical fitness/or (physical activity or exercise or fitness or cardiovascular training or strength training or aerobic exercise or resistance training or physical fitness).ti, ab.) and (comorbidity/or chronic disease/or multimorbidity.ti, ab. or “multiple chronic conditions”.ti, ab. or “multiple long-term conditions”.ti, ab.) and (artificial intelligence/or machine learning/or deep learning/or natural language processing/or “large language models”.ti, ab. or llm.ti, ab.) and (intervention or program or promotion or “health behavior” or “digital health”).ti, ab. | 63 |
| CINAHL | ((MH “Exercise+”) OR (MH “Physical Activity”) OR “physical activity” OR “exercise intervention” OR “aerobic training” OR “resistance training”) AND ((MH “Comorbidity”) OR “multimorbidity” OR “chronic disease” OR “multiple chronic conditions”) AND ((MH “Artificial Intelligence”) OR “machine learning” OR “deep learning” OR “natural language processing” OR “large language model” OR “LLM”) AND (“intervention” OR “digital health”) |
3 |
| Cochrane Library | (“physical activity” OR “exercise intervention” OR “aerobic training” OR “resistance training”) AND (“comorbidity” OR “multimorbidity” OR “chronic disease” OR “multiple chronic conditions”) AND (“artificial intelligence” OR “machine learning” OR “deep learning” OR “natural language processing” OR “large language model” OR “LLM”) AND (“intervention” OR “digital health”) |
1 review, 19 trials |
| Medline (Ovid) | (exp Exercise/or exp Motor Activity/or exp Physical Fitness/or (physical activity or exercise or fitness or “cardiovascular training” or “strength training” or “aerobic exercise” or “resistance training” or “physical fitness”).ti, ab.) and (exp Comorbidity/or exp Multimorbidity/or (multimorbidity or comorbidity or “multiple chronic conditions” or “multiple long-term conditions”).ti, ab.) and (exp Artificial Intelligence/or exp Machine Learning/or exp Deep Learning/or exp Natural Language Processing/or (“artificial intelligence” or “machine learning” or “deep learning” or “natural language processing” or “large language models” or LLM).ti, ab.) and (intervention or program or promotion or “health behavior”).ti, ab. | 10 |
| Scopus | TITLE-ABS-KEY( ( “physical activity” OR “exercise intervention” OR “aerobic training” OR “resistance training” ) AND ( comorbidity OR multimorbidity OR “chronic disease” OR “multiple chronic conditions” ) AND ( “artificial intelligence” OR “machine learning” OR “deep learning” OR “natural language processing” OR “large language model” OR LLM ) AND ( intervention OR “digital health” ) ) |
109 |
| PsychINFO | (physical activity OR exercise OR fitness OR movement OR cardiovascular training OR strength training OR aerobic exercise OR resistance training OR physical fitness) AND (multimorbidity OR comorbidity, OR multiple chronic conditions OR multiple long-term conditions) AND (artificial intelligence OR machine learning OR deep learning OR natural language processing OR large language models OR LLM*) | 36 |
| PubMed | ((“Exercise”[MeSH Terms] OR “Exercise Therapy”[MeSH Terms] OR “physical activity”[Title/Abstract] OR “exercise intervention”[Title/Abstract] OR “aerobic training”[Title/Abstract] OR “resistance training”[Title/Abstract]) AND (“Comorbidity”[MeSH Terms] OR “chronic disease”[MeSH Terms] OR “comorbidity”[Title/Abstract] OR “multimorbidity”[Title/Abstract] OR “multiple chronic conditions”[Title/Abstract] OR “chronic illness”[Title/Abstract]) AND (“Artificial Intelligence”[MeSH Terms] OR “machine learning”[Title/Abstract] OR “deep learning”[Title/Abstract] OR “natural language processing”[Title/Abstract] OR “large language model”[Title/Abstract] OR “LLM”[Title/Abstract]) AND (“intervention”[Title/Abstract] OR “digital health”[Title/Abstract])) |
35 |
Appendix B. Data Extraction Table of Included Studies
Available at: OSF | Exercise Rapid Review Included Papers - Sheet1 (2).pdf
References
- Smith, SM; Wallace, E; O’Dowd, T; et al. Interventions for improving outcomes in patients with multimorbidity in primary care and community settings. Cochrane Database Syst Rev. 2021, 1(1). [Google Scholar] [CrossRef] [PubMed]
- Western, MJ; Armstrong, MEG; Islam, I; et al. The effectiveness of digital interventions for increasing physical activity in individuals of low socioeconomic status: a systematic review and meta-analysis. Int J Behav Nutr Phys Act. 2021, 18(1), 148. [Google Scholar] [CrossRef] [PubMed]
- Zangger, G; Bricca, A; Liaghat, B; et al. Benefits and harms of digital health interventions promoting physical activity in people with chronic conditions: systematic review and meta-analysis. J Med Internet Res 2023, 25. [Google Scholar] [CrossRef] [PubMed]
- Young, HML; Yates, T; Dempsey, PC; et al. Physical activity and sedentary behaviour interventions for people living with both frailty and multiple long-term conditions: a scoping review protocol. BMJ Open. Published. 2022, 12(5), e061104. [Google Scholar] [CrossRef] [PubMed]
- Jørgensen, LB; Bricca, A; Bernhardt, A; Juhl, CB; Tang, LH; Mortensen, SR; Eriksen, JA; Walløe, S; Skou, ST. Objectively measured physical activity levels and adherence to physical activity guidelines in people with multimorbidity-A systematic review and meta-analysis. PLoS One 2022, 17(10), e0274846. [Google Scholar] [CrossRef] [PubMed]
- Sutton, RT; Pincock, D; Baumgart, DC; et al. An overview of clinical decision support systems: benefits, risks, and strategies for success. NPJ Digit Med 2020, 3, 17. [Google Scholar] [CrossRef] [PubMed]
- Torous, J; Jän Myrick, K; Rauseo-Ricupero, N; et al. Digital mental health and COVID-19: using technology today to accelerate the curve on access and quality tomorrow. JMIR Ment Health 2020, 7(3). [Google Scholar] [CrossRef] [PubMed]
- Sumner, J; Lim, HW; Chong, LS; et al. Artificial intelligence in physical rehabilitation: a systematic review. Artif Intell Med. 2023, 146, 102693. [Google Scholar] [CrossRef] [PubMed]
- Chaparala, SP; Pathak, KD; Dugyala, RR; et al. Leveraging artificial intelligence to predict and manage complications in patients with multimorbidity: a literature review. Cureus 2025, 17(1). [Google Scholar] [CrossRef] [PubMed]
- Bricca, A; Harris, LK; Jäger, M; et al. Benefits and harms of exercise therapy in people with multimorbidity: a systematic review and meta-analysis of randomised controlled trials. Ageing Res Rev. [CrossRef] [PubMed]
- Dibben, GO; Gardiner, L; Young, HML; Wells, V; Evans, RA; Ahmed, Z; Barber, S; Dean, S; Doherty, P; Gardiner, N; Greaves, C; Ibbotson, T; Jani, BD; Jolly, K; Mair, FS; McIntosh, E; Ormandy, P; Simpson, SA; Ahmed, S; Krauth, SJ; Steell, L; Singh, SJ; Taylor, RS. PERFORM research team. Evidence for exercise-based interventions across 45 different long-term conditions: an overview of systematic reviews. EClinicalMedicine 2024, 72, 102599. [Google Scholar] [CrossRef] [PubMed]
- Tricco, AC; Lillie, E; Zarin, W; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann Intern Med. 2018, 169(7), 467–473. [Google Scholar] [CrossRef] [PubMed]
- Øverås, CK; Nilsen, TIL; Nicholl, BI; Rughani, G; Wood, K; Søgaard, K; et al. Multimorbidity and co-occurring musculoskeletal pain do not modify the effect of the selfBACK app on low back pain-related disability. [CrossRef] [PubMed]
- Broadbent, E; Garrett, J; Jepsen, N; Li Ogilvie, V; Ahn, HS; Robinson, H; et al. Using Robots at Home to Support Patients with Chronic Obstructive Pulmonary Disease: Pilot Randomised Controlled Trial. Journal of Medical Internet Research 2018, 20(2). [Google Scholar] [CrossRef] [PubMed]
- Liu, Q; Zhang, Y. Advanced resistance exercise combined with aerobic rehabilitation training on cardiopulmonary function. Molecular & Cellular Biomechanics 2024, 21(1), 186. [Google Scholar] [CrossRef]
- Carrasco-Hernandez, L; Jódar-Sánchez, F; Núñez-Benjumea, F; Moreno Conde, J; Mesa González, M; Civit-Balcells, A; et al. A Mobile Health Solution Complementing Psychopharmacology-Supported Smoking Cessation: Randomised Controlled Trial. JMIR mHealth and uHealth 2020, 8(4), e17530. [Google Scholar] [CrossRef] [PubMed]
- Letton, ME; Trần, Thái Bình; Flower, S; Wewege, MA; Wang, Amanda Ying; Sandler, CX; et al. Digital Physical Activity and Exercise Interventions for People Living with Chronic Kidney Disease: A Systematic Review of Health Outcomes and Feasibility. Journal of Medical Systems 2024, 48(1). [Google Scholar] [CrossRef]
Figure 1.
PRISMA flow diagram of study selection. Adapted PRISMA flowchart illustrating the identification, screening, eligibility assessment, and inclusion process for the review. Records were identified from seven databases (BASE, CINAHL, Cochrane Library, OVID, Scopus, PsycINFO, and PubMed), with duplicates removed prior to screening. A total of 227 records were screened, resulting in 4 studies being included in the final review.
Figure 1.
PRISMA flow diagram of study selection. Adapted PRISMA flowchart illustrating the identification, screening, eligibility assessment, and inclusion process for the review. Records were identified from seven databases (BASE, CINAHL, Cochrane Library, OVID, Scopus, PsycINFO, and PubMed), with duplicates removed prior to screening. A total of 227 records were screened, resulting in 4 studies being included in the final review.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).
Copyright: This open access article is published under a Creative Commons CC BY 4.0 license, which permit the free download, distribution, and reuse, provided that the author and preprint are cited in any reuse.